Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: glp-2

GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically

GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically

September 14, 2026/0 Comments/in Uncategorized/by

Fewer than 5% of people with obesity currently have access to the drug class generating the most clinical excitement since statins, yet the peptide research space has expanded far beyond that single drug class, creating genuine confusion about what is approved, what is investigational, and what remains largely theoretical. Understanding GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically is not just an academic exercise. It shapes how clinicians, researchers, and informed readers interpret headlines, evaluate compounds, and distinguish between a regulated medicine and a laboratory tool.

Key Takeaways

  • GLP-1 receptor agonists are an established, FDA-approved drug class; retatrutide is a next-generation triple agonist still moving through Phase 3 trials as of 2026.
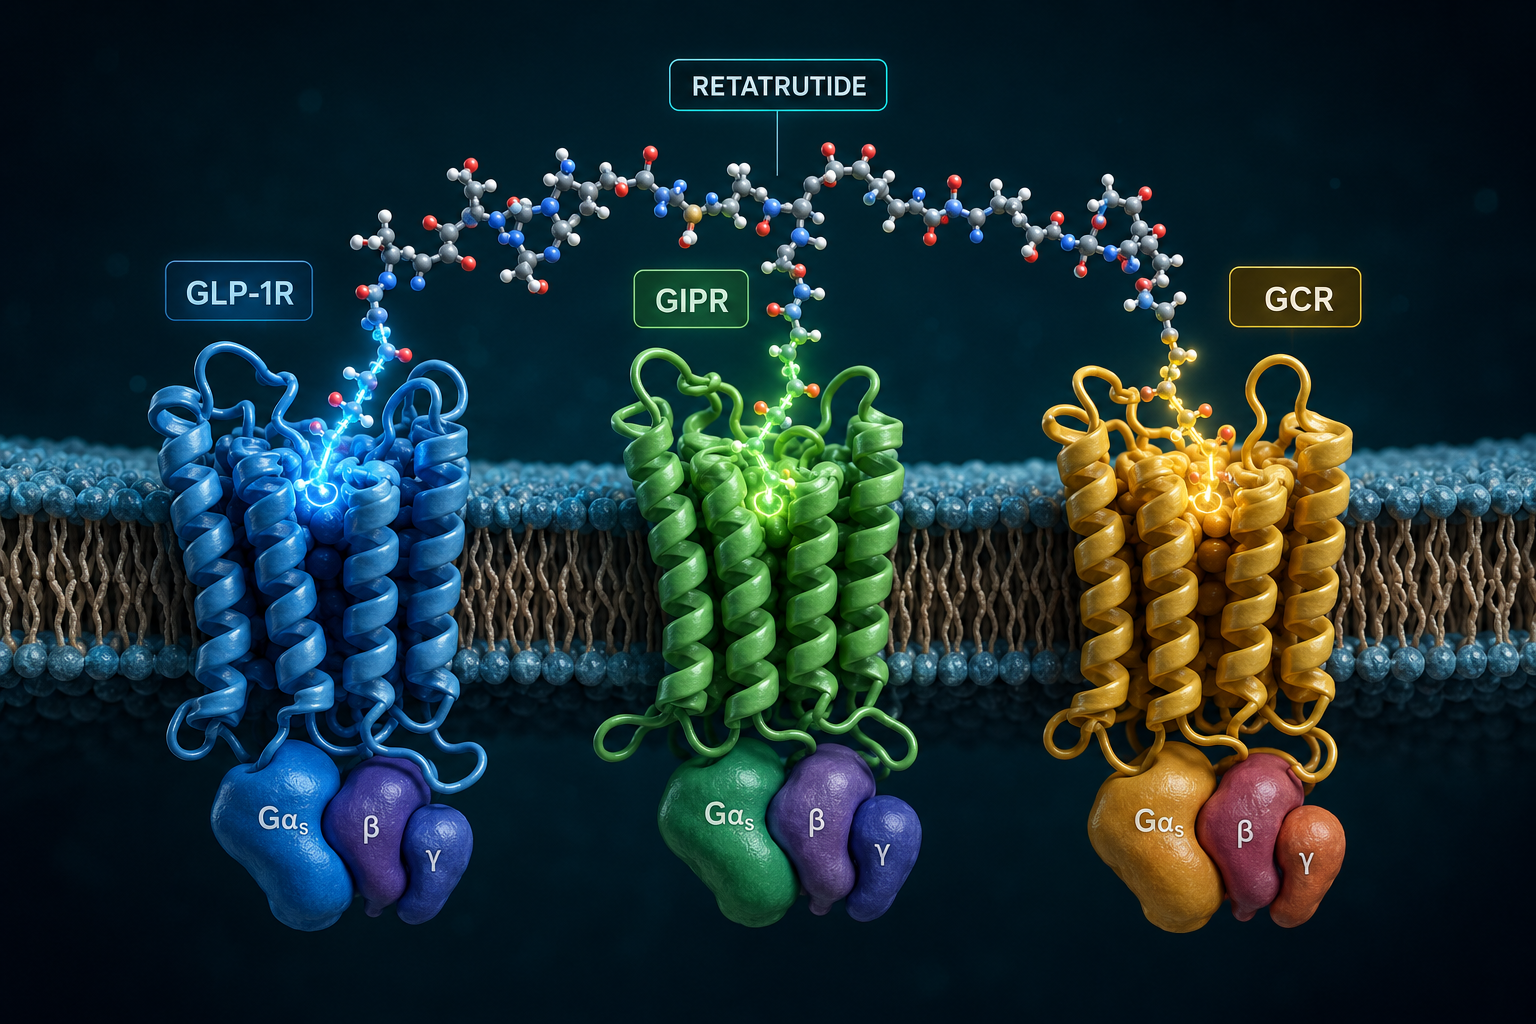
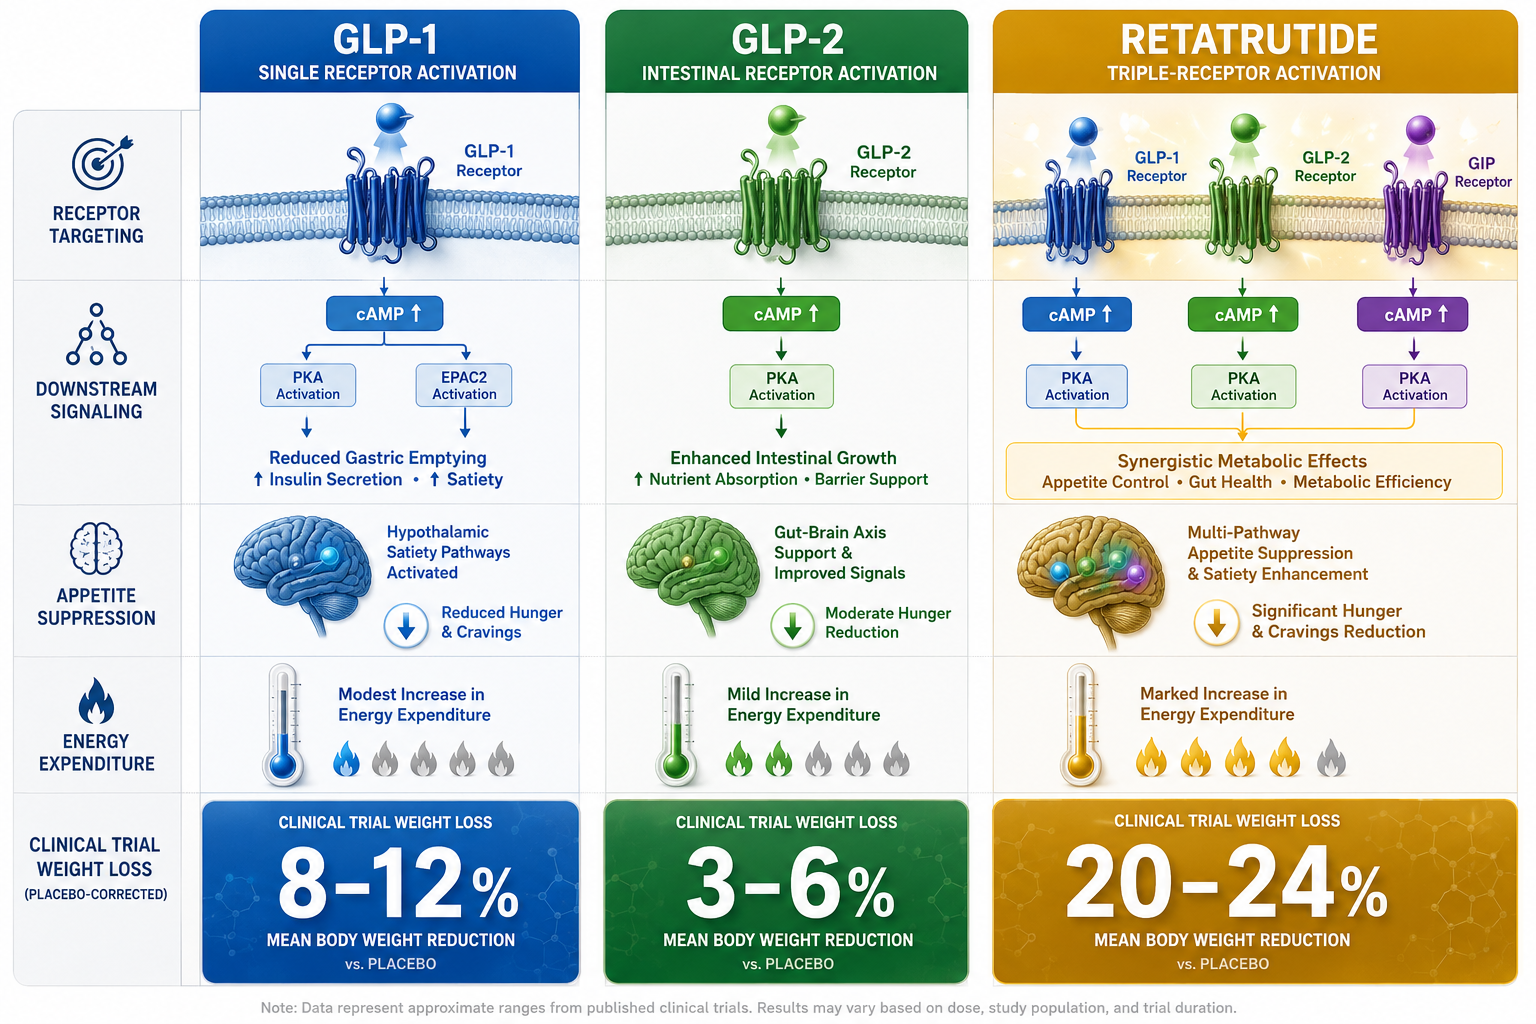
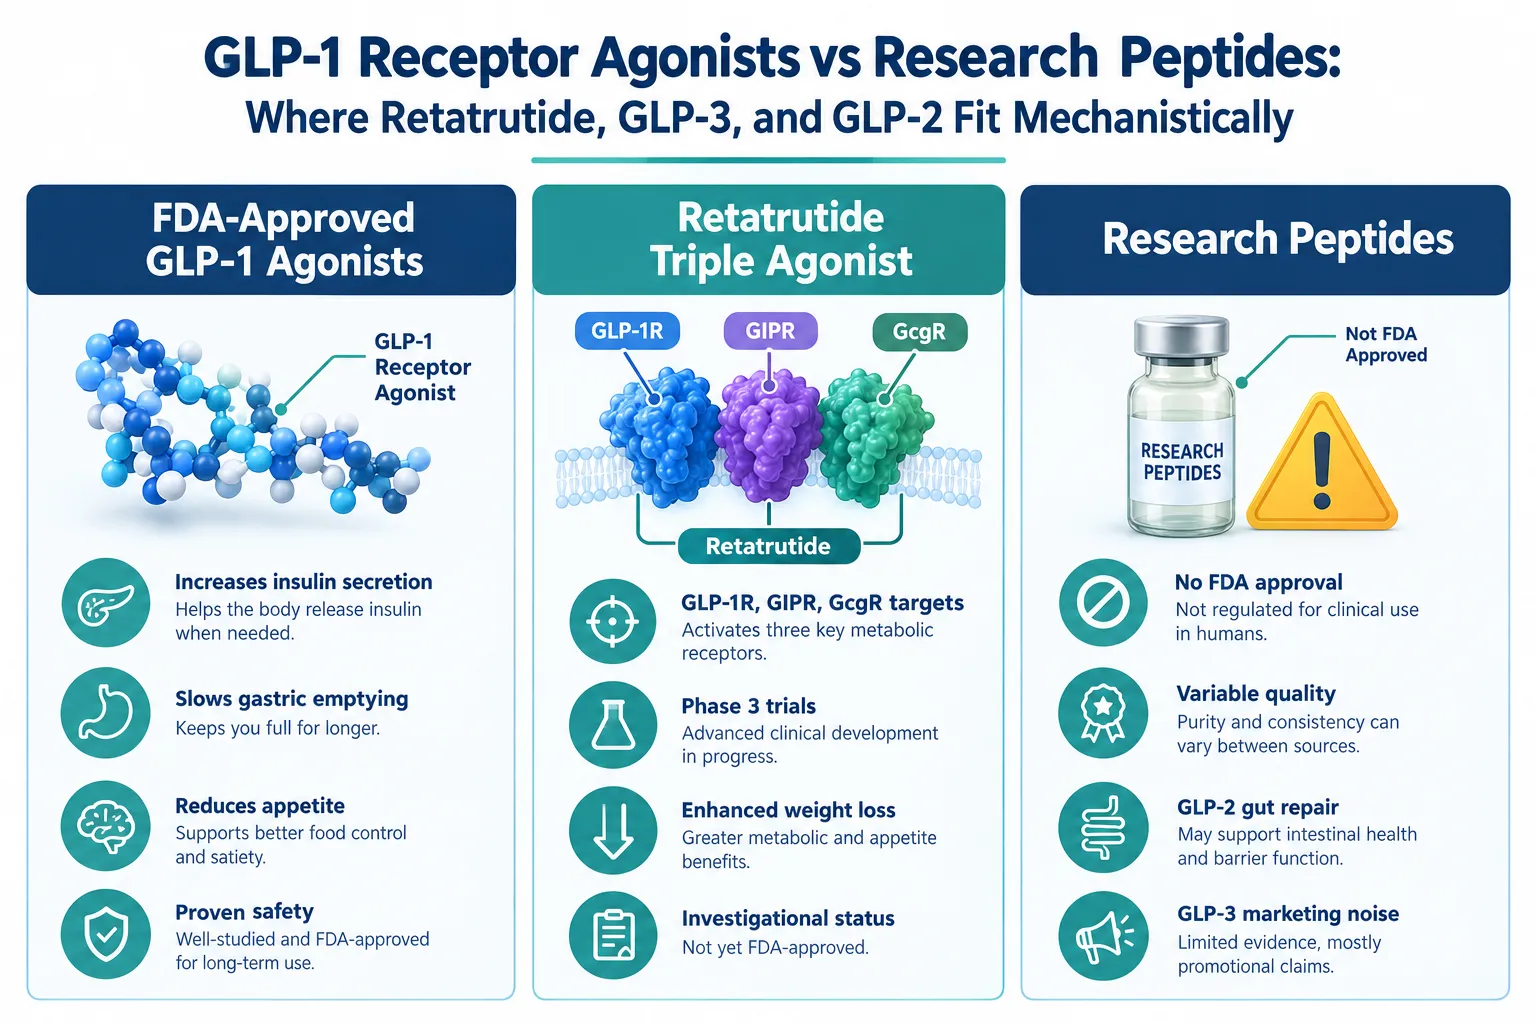
  • Retatrutide targets three receptors (GLP-1R, GIPR, and GcgR simultaneously), producing weight-loss results that significantly exceed standard GLP-1 monotherapy in Phase 2 data.
  • GLP-2 is a structurally related peptide with a distinct, gut-focused mechanism; its agonists are approved for specific intestinal conditions, not obesity.
  • "GLP-3" does not currently represent a validated receptor class; the term is largely used in marketing contexts and should be treated with caution.
  • Research peptides occupy a separate regulatory and mechanistic category from approved GLP-1 drugs, and the distinction matters for both safety and scientific accuracy.

What Defines a GLP-1 Receptor Agonist

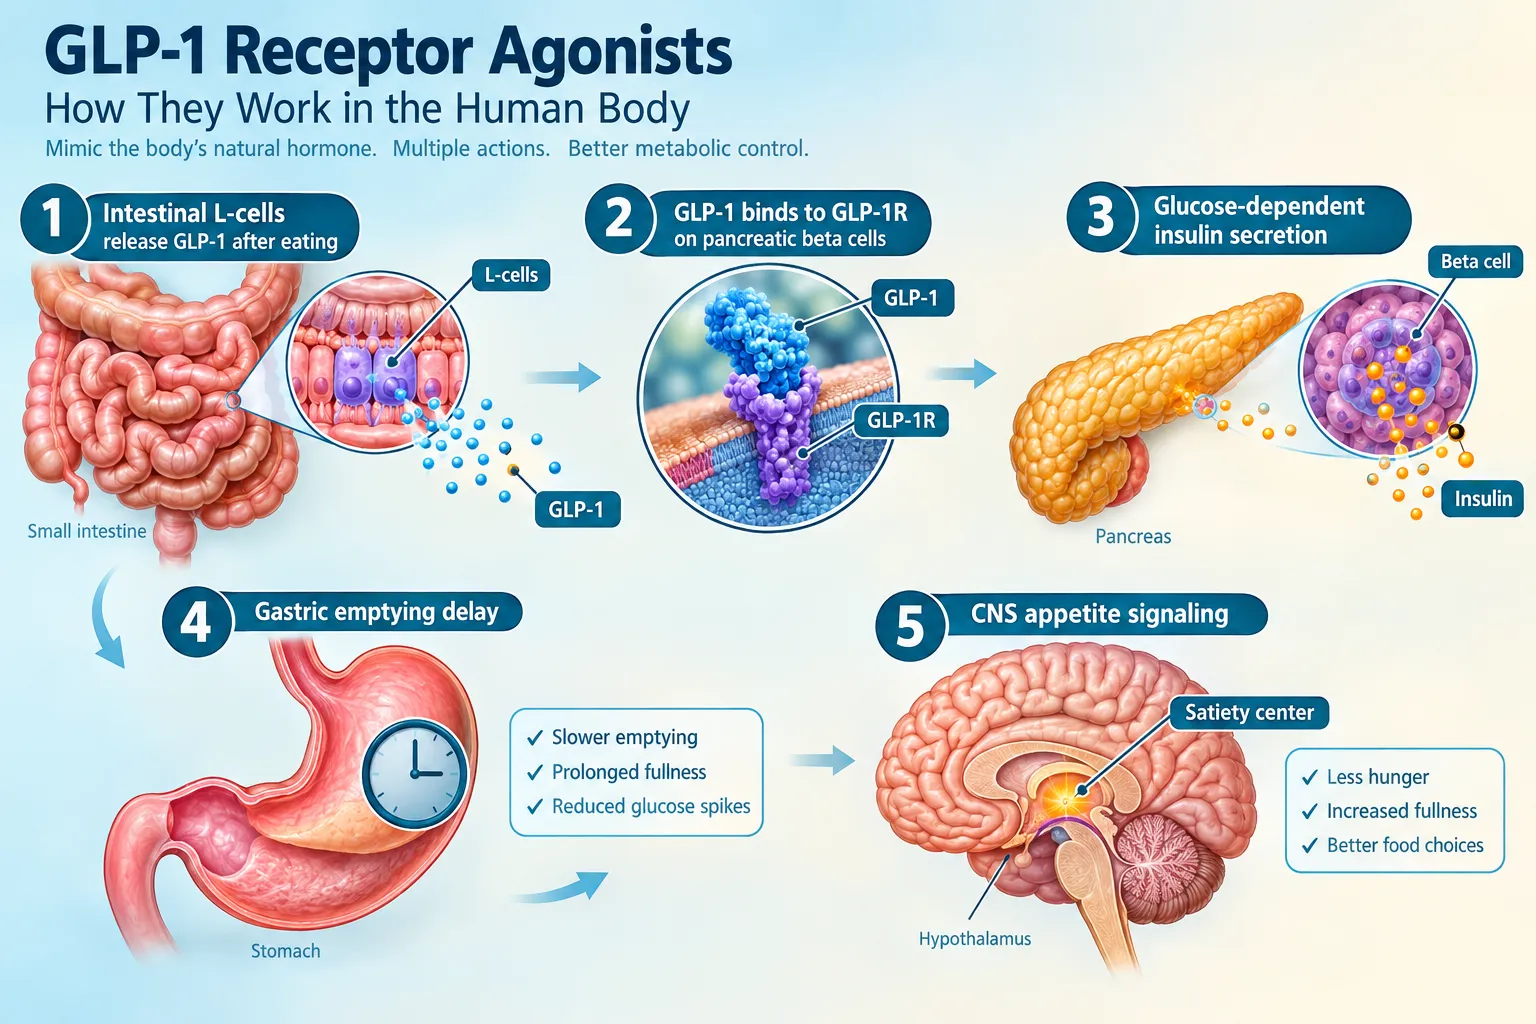
GLP-1 (glucagon-like peptide-1) is an incretin hormone released from intestinal L-cells after eating. It binds the GLP-1 receptor (GLP-1R) to stimulate glucose-dependent insulin secretion, suppress glucagon, slow gastric emptying, and reduce appetite through central nervous system signaling.

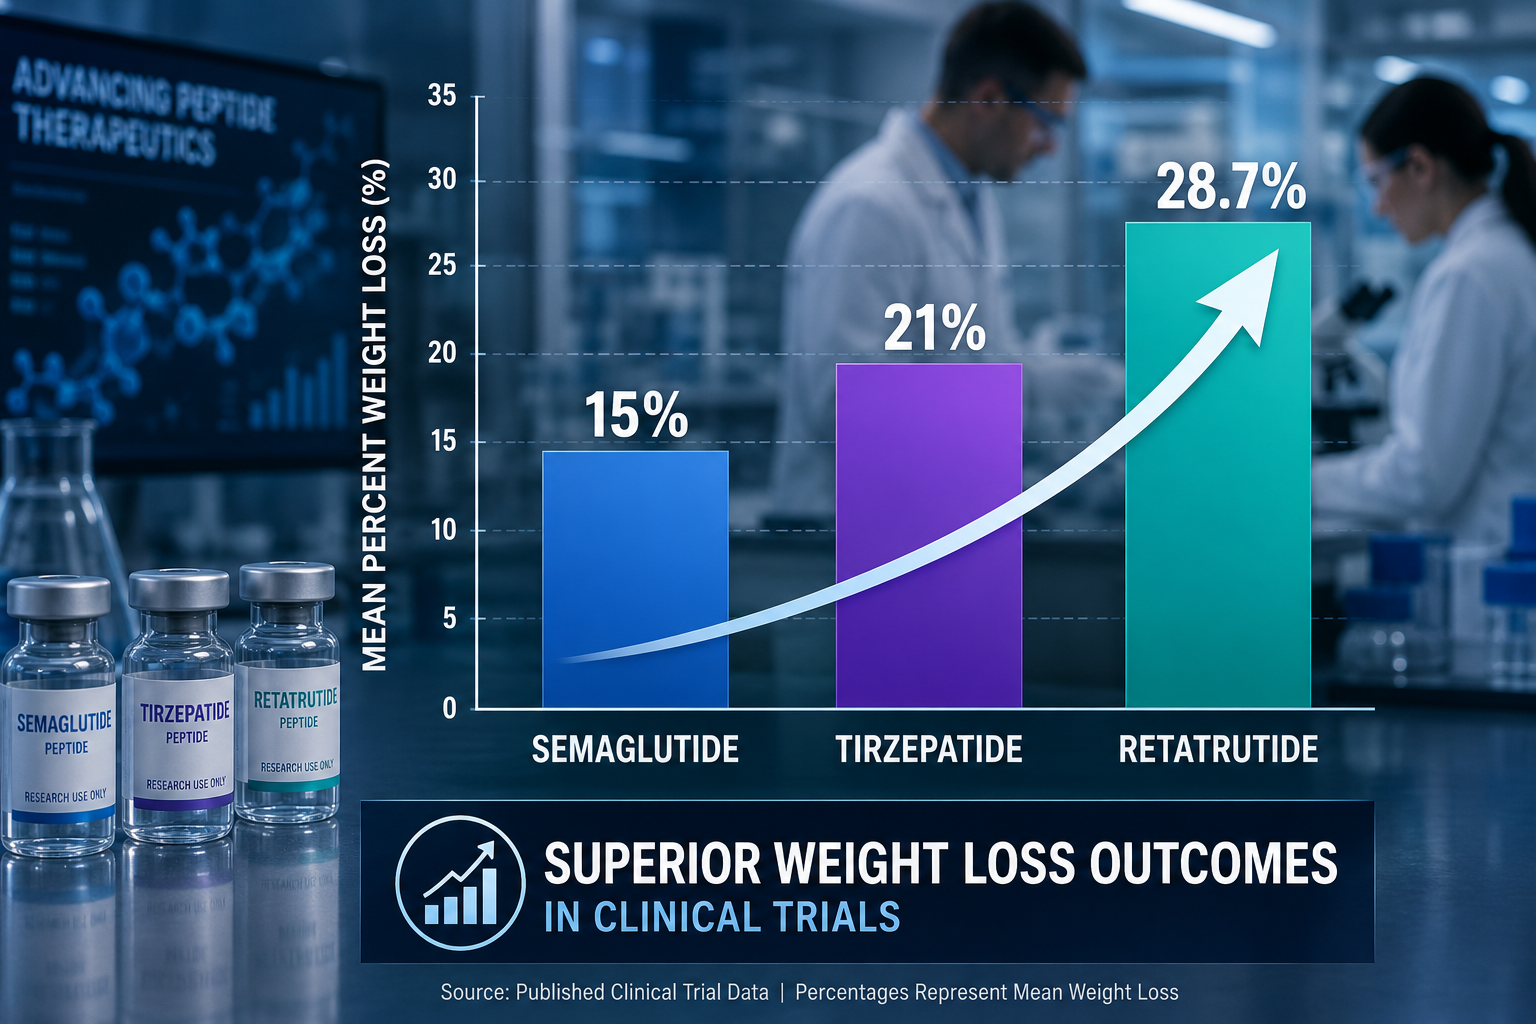
Approved GLP-1 receptor agonists, including semaglutide and liraglutide, are synthetic analogs engineered for extended half-lives. They are regulated medicines with defined dosing, safety profiles, and clinical indications. In obesity trials, semaglutide produces mean body-weight reductions of approximately 15% over 68 weeks, a benchmark that defined the class.
What Defines a GLP-1 Receptor Agonist

The key mechanistic point: these drugs act on a single receptor. Their benefits, glycemic control, modest cardiovascular risk reduction, and weight loss, flow from that one target. This single-receptor architecture is precisely what newer compounds like retatrutide are designed to move beyond.

Retatrutide: Where Triple Agonism Changes the Equation

Retatrutide is the clearest example of why the comparison of GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically demands precision. It is not a research peptide in the informal sense. It is an investigational drug in structured clinical development, and its mechanism is meaningfully different from standard GLP-1 monotherapy.

Retatrutide simultaneously activates three receptors:

Receptor Primary Action
GLP-1R Appetite suppression, insulin secretion, gastric slowing
GIPR (GIP receptor) Enhanced insulin response, adipose tissue signaling
GcgR (Glucagon receptor) Increased energy expenditure, thermogenesis, hepatic fat reduction

This triple agonism produced striking Phase 2 results: participants receiving the highest dose achieved mean weight reductions of approximately 24% over 48 weeks, roughly 60% greater than semaglutide benchmarks in comparable timeframes. Responder analysis showed that a substantial proportion of participants lost more than 20% of body weight, a threshold rarely crossed with single-receptor agents.

Beyond weight, Phase 2 data showed meaningful reductions in fasting glucose, triglycerides, LDL particle counts, and blood pressure. These cardiometabolic improvements suggest the glucagon receptor component contributes effects beyond appetite suppression alone.

As of 2026, retatrutide is in Phase 3 trials covering obesity, type 2 diabetes, and non-alcoholic steatohepatitis (NASH). Regulatory submission timelines remain under active review. Researchers tracking this compound can find relevant context on retatrutide clinical trials and the broader retatrutide clinical trial landscape.

For those looking at investigational compound options, buy Reta online resources and buy Reta peptide listings are available for research purposes, distinct from clinical use.

GLP-2 and GLP-3: Mechanistic Niches and Marketing Noise
GLP-2 and GLP-3: Mechanistic Niches and Marketing Noise

GLP-2: A Real Peptide With a Distinct Gut Role

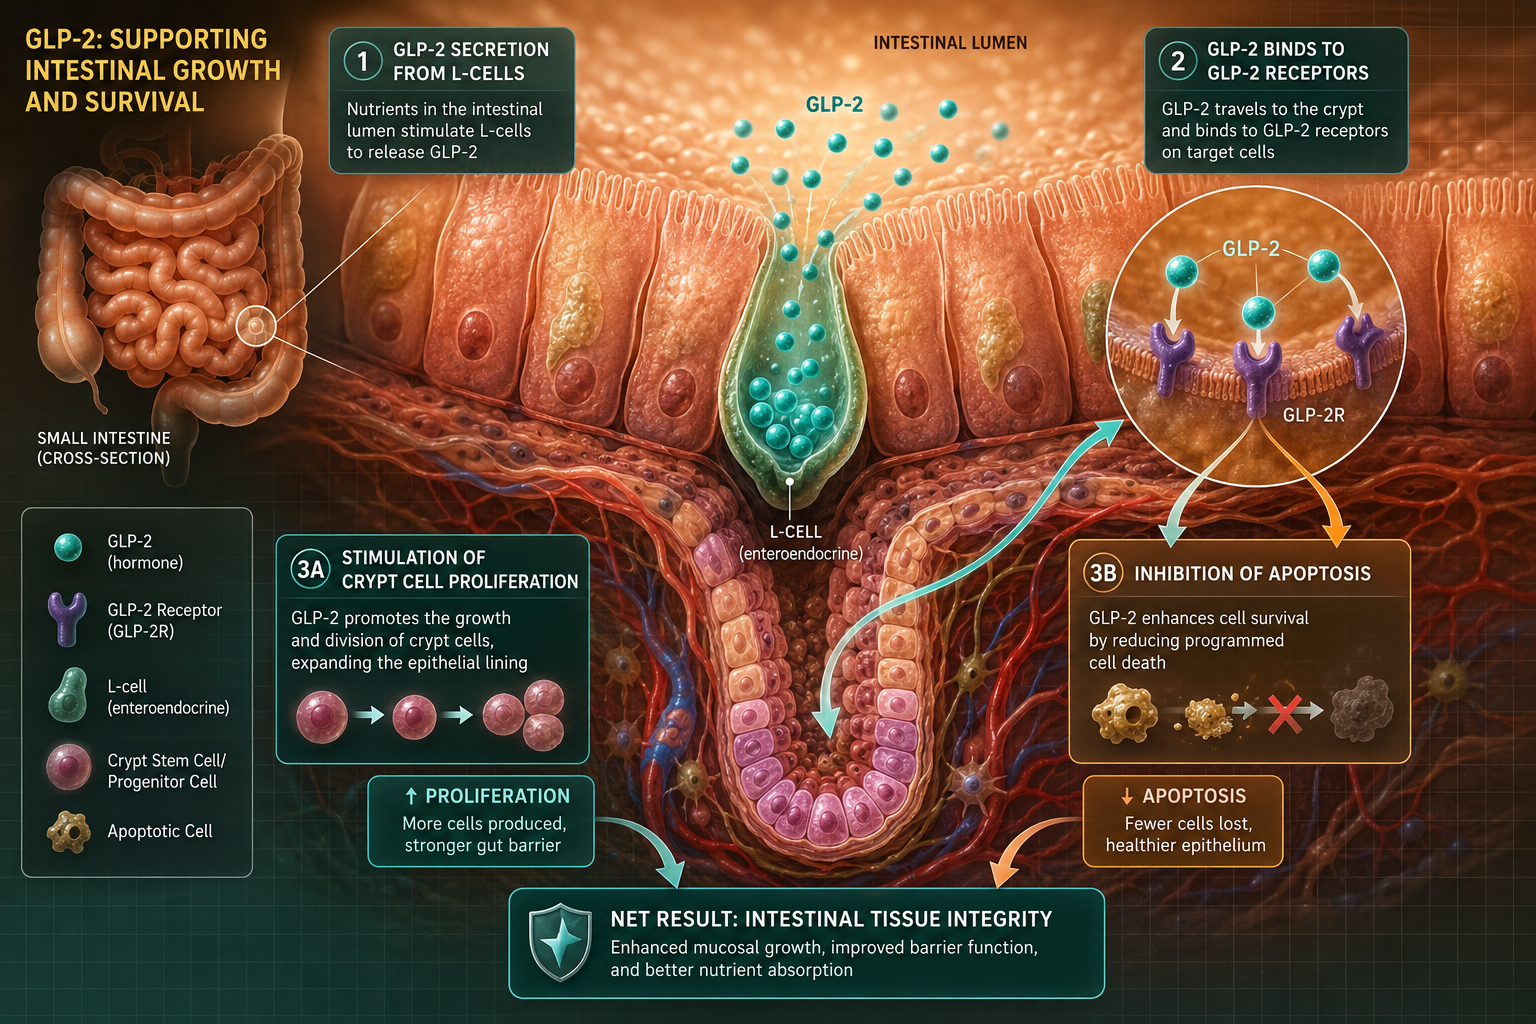
GLP-2 is co-secreted with GLP-1 from the same intestinal L-cells, but it acts on a completely separate receptor (GLP-2R) with no meaningful overlap in function. Its primary actions are:

  • Intestinal epithelial growth, stimulating mucosal repair and villus elongation
  • Nutrient absorption enhancement, increasing gut surface area
  • Reduced intestinal permeability, supporting barrier integrity

GLP-2 agonists such as teduglutide are approved for short bowel syndrome, a condition where intestinal absorptive surface is critically reduced. Apraglutide is in late-stage development for similar indications. These are not weight-loss drugs. They do not activate GLP-1R, do not suppress appetite centrally, and are not interchangeable with incretin therapies. Placing GLP-2 agonists in the same category as semaglutide or retatrutide reflects a fundamental mechanistic misunderstanding.

For those interested in the gut-focused metabolic research space, tesa peptide benefits and the broader where to buy tesa online resource offer adjacent context on peptides that influence metabolic tissue.

GLP-3: Conceptual Label, Not an Established Class

"GLP-3" appears in product marketing and some preliminary literature, but it does not currently represent a validated receptor class with confirmed pharmacology. The peptide fragment sometimes labeled GLP-3 is a further processing product of proglucagon, but no confirmed GLP-3 receptor has been characterized with reproducible, peer-reviewed receptor binding data.

"GLP-3 as a drug target remains conceptual. Researchers should treat any product marketed under this label with significant skepticism until receptor confirmation and clinical data exist."

This is a critical distinction in the broader discussion of GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically. Mixing a well-validated drug class with a label that lacks receptor confirmation creates confusion that can mislead both researchers and consumers.

For those exploring GLP-3-related research compounds, the GLP-3R 30mg peptide GA9 and GLP-3 Reta 30mg for sale listings provide research-grade options, while GLP3 where to buy resources offer sourcing guidance for laboratory investigation contexts.

Regulatory Status and the Research Peptide Distinction

Regulatory Status and the Research Peptide Distinction

The regulatory gap between approved GLP-1 receptor agonists and research peptides is substantial and consequential.

Approved GLP-1 RAs:

  • Manufactured under GMP (Good Manufacturing Practice) standards
  • Carry defined pharmacokinetic and safety profiles from large-scale trials
  • Prescribed by licensed clinicians for specific indications
  • Subject to post-market surveillance

Research peptides (including investigational GLP-related compounds):

  • Intended for laboratory and preclinical research use only
  • Not approved for human therapeutic use outside clinical trials
  • Purity and characterization depend entirely on supplier quality
  • Regulatory oversight varies significantly by jurisdiction

Retatrutide occupies a middle position: it is investigational, not approved, but it is studied under strict IND (Investigational New Drug) frameworks with rigorous safety monitoring, a very different context from informal research peptide use.

The safety profile of retatrutide in Phase 2 and early Phase 3 data mirrors the GLP-1 class in its most common adverse events: nausea, vomiting, and gastrointestinal discomfort, predominantly dose-dependent and transient. No novel safety signals have emerged that are categorically distinct from the established GLP-1 agonist class, though the glucagon agonism component warrants continued monitoring for effects on bone density and hepatic function.

For researchers sourcing lab tested peptides and evaluating supplier quality, purity documentation is non-negotiable. The visceral fat research tag provides additional context on metabolic endpoints relevant to GLP-related compound investigation.

Conclusion

The landscape of GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically is not as complicated as the terminology suggests, but it does require precision. Three actionable principles apply:

  1. Distinguish by receptor and regulatory status. GLP-1 RAs are approved, single-receptor drugs. Retatrutide is a triple agonist in Phase 3 development. GLP-2 agonists address gut integrity, not obesity. GLP-3 lacks confirmed receptor biology.

  2. Evaluate mechanistic claims critically. Any compound marketed as a "GLP-3 agonist" without peer-reviewed receptor confirmation deserves scrutiny. Receptor identity is the foundation of pharmacological classification.

  3. Apply the research-peptide standard. For laboratory investigation, source purity-verified, lab-tested compounds from documented suppliers. Never conflate research use with clinical therapy.

As Phase 3 retatrutide data matures through 2026 and beyond, the gap between triple agonism and standard GLP-1 monotherapy will become clearer. Staying grounded in mechanism, not marketing, is the most reliable guide through this rapidly evolving field.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/glp-1-receptor-agonists-vs-research-peptides-where-retatrutide-glp-3-and-glp-2-f.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:07:022026-09-14 13:07:02GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically
Peptide Research and Omeprazole: What Acid-Suppressing Drugs Mean for GLP-2 and Gut-Focused Studies

Peptide Research and Omeprazole: What Acid-Suppressing Drugs Mean for GLP-2 and Gut-Focused Studies

September 14, 2026/0 Comments/in Uncategorized/by

More than 15 percent of adults in Western countries take a proton pump inhibitor (PPI) like omeprazole on a regular basis, yet this common medication rarely appears as a controlled variable in gut-focused peptide trials. That gap matters more than most researchers realize. Understanding peptide research and omeprazole interactions, especially what acid-suppressing drugs mean for GLP-2 and gut-focused studies, is quickly becoming a prerequisite for designing credible intestinal peptide protocols in 2026.

Key Takeaways

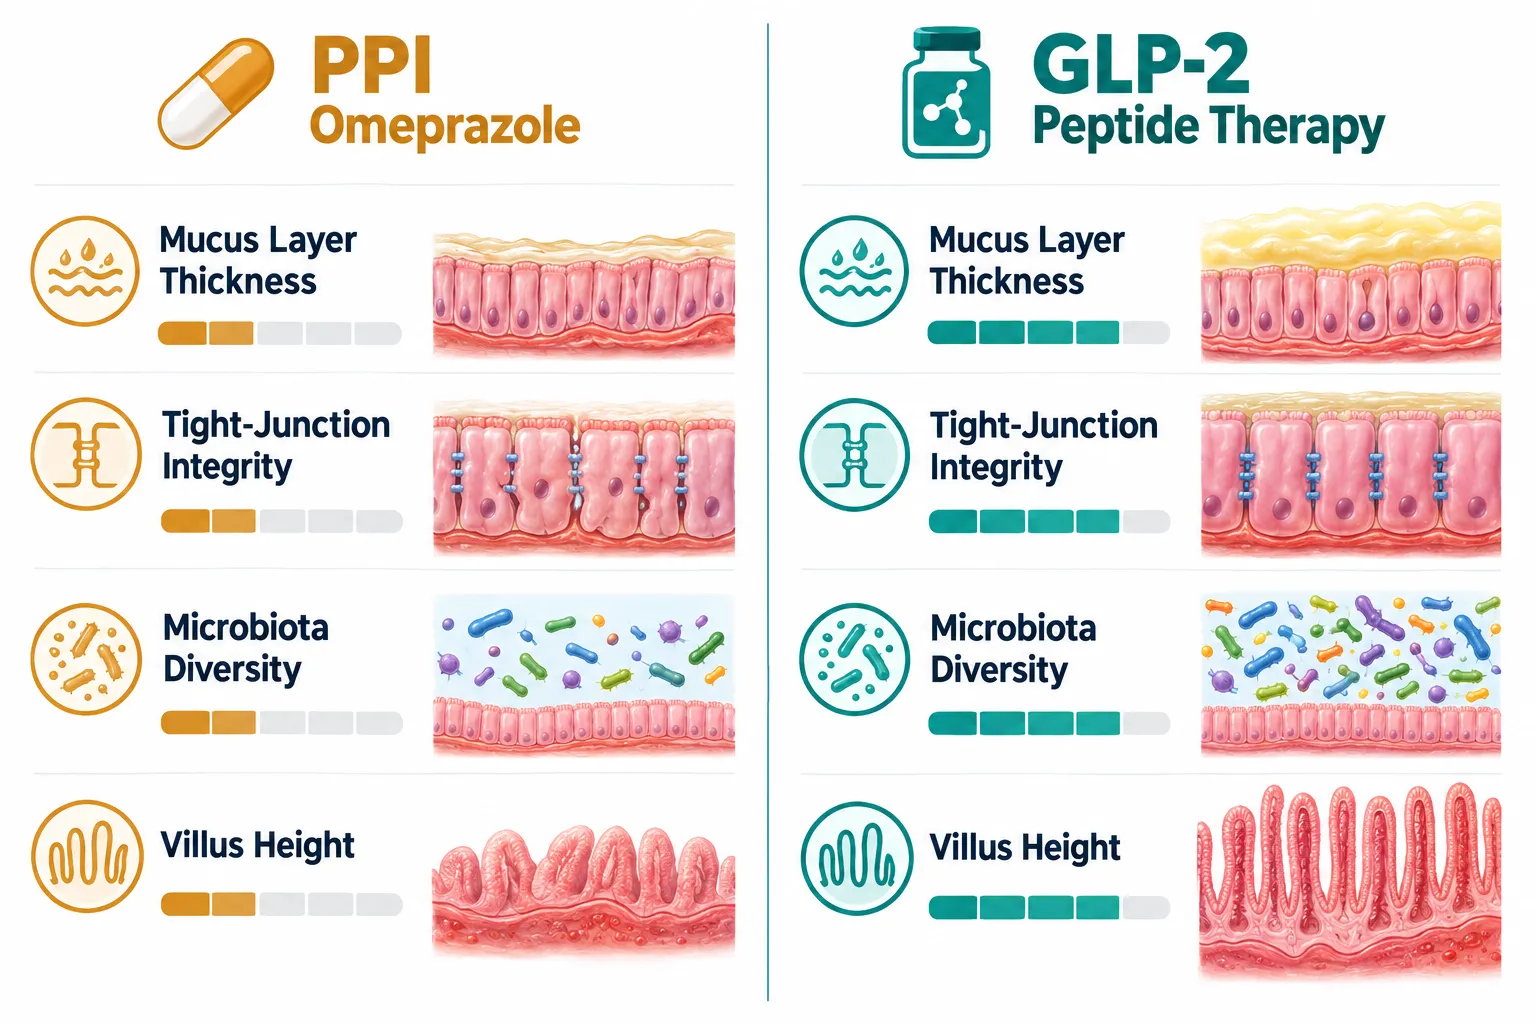
  • Omeprazole and other PPIs modestly improve gut barrier function, but GLP-2 peptides produce significantly larger gains in villus height and tight-junction integrity through distinct downstream mechanisms.
  • Pharmacokinetic data show omeprazole does not meaningfully blunt GLP-peptide exposure; any increase in drug absorption is small and clinically irrelevant.
  • Long-term PPI use reduces gut microbiota diversity, while GLP-2 therapy is linked to more favorable microbiota profiles, making PPI status a critical covariate in intestinal studies.
  • Oral peptide formulations should follow an empty-stomach dosing window, with PPI administration delayed by at least 30 minutes to protect bioavailability.
  • Future GLP-2 and teduglutide trials are expected to treat chronic PPI use as a pre-specified variable or exclusion criterion to isolate peptide-driven mucosal effects.

How Omeprazole Affects the Gut Environment Relevant to Peptide Research

How Omeprazole Affects the Gut Environment Relevant to Peptide Research

Omeprazole works by irreversibly blocking the hydrogen-potassium ATPase enzyme in gastric parietal cells, suppressing acid output and raising gastric pH. That pH shift creates downstream changes throughout the gastrointestinal tract, changes that overlap with the very endpoints gut-focused peptide studies are designed to measure.

What PPIs do to the gut environment:

  • Modestly increase mucus layer thickness
  • Improve tight-junction integrity by reducing acid-driven mucosal injury
  • Raise gastric pH, which can affect the absorption window for orally administered compounds
  • With long-term use, reduce gut microbiota diversity, a recognized risk in chronic PPI therapy
  • Associate with a small but statistically significant increase in gastric cancer risk over 10 years (number needed to harm approximately 1,191 over a decade)

PPIs also carry documented risks including infection susceptibility and nutrient malabsorption. These effects are not trivial in a research context. When a participant is taking omeprazole daily, the baseline gut environment is already shifted, and that shift can confound mucosal endpoints in any gut-focused peptide study.

Key point: PPIs and GLP-2 peptides act on overlapping but not identical gut endpoints. Failing to account for PPI use in study design risks attributing PPI-driven changes to the peptide under investigation.

GLP-2 Mechanisms Compared to Acid Suppression

GLP-2 Mechanisms Compared to Acid Suppression

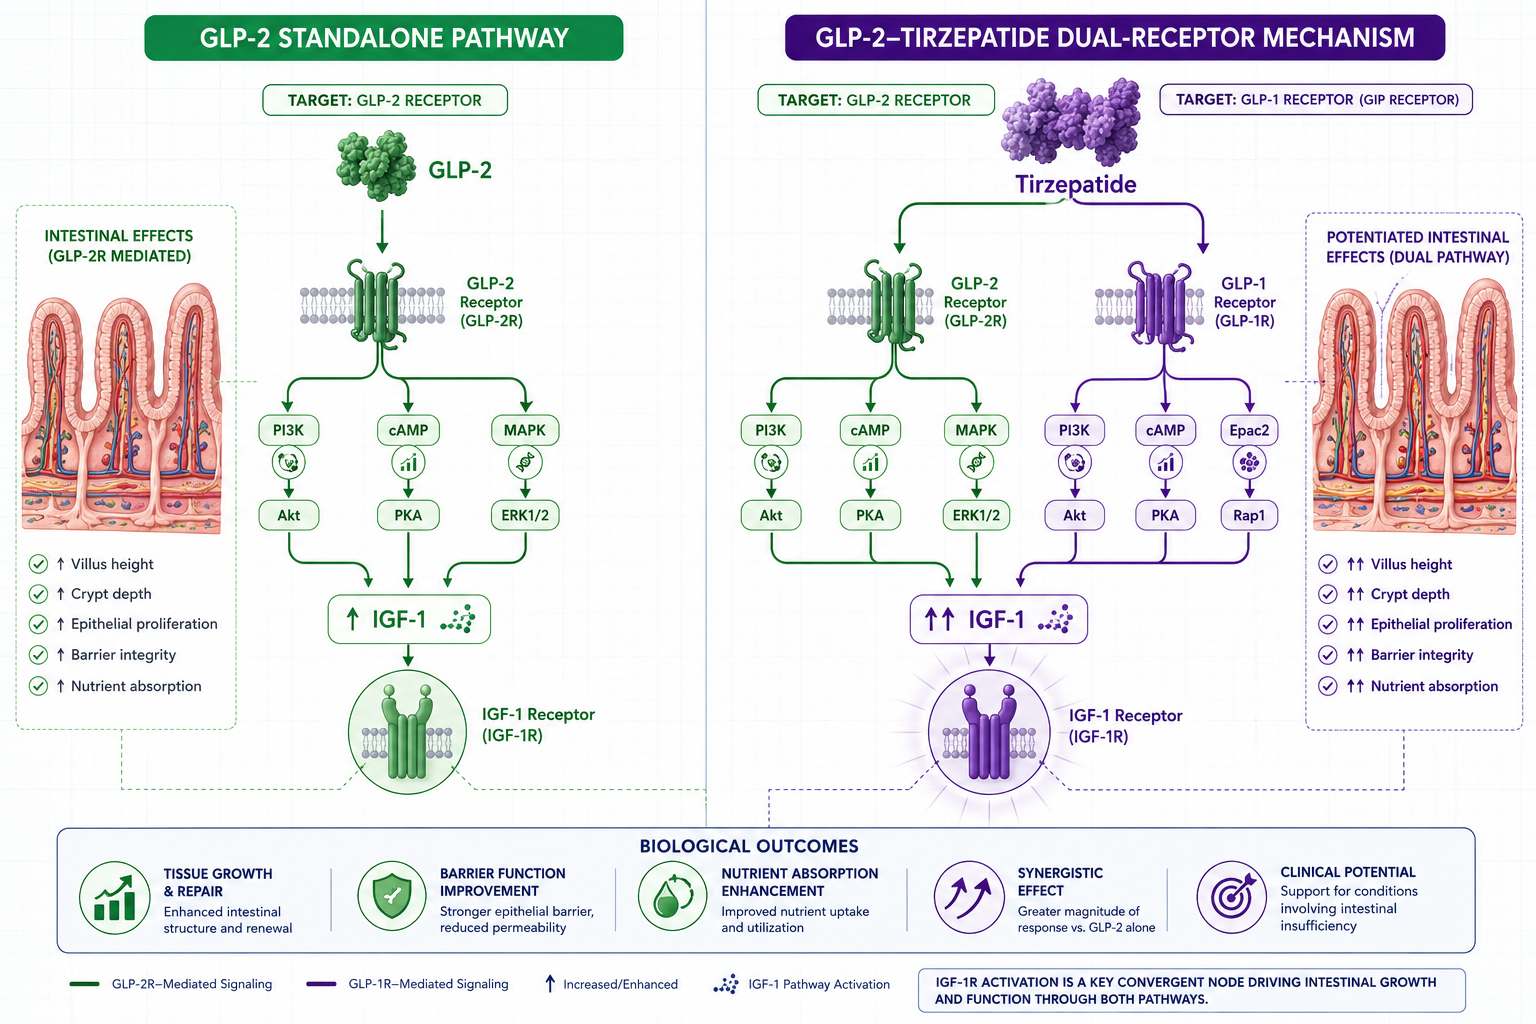
GLP-2 (glucagon-like peptide-2) and its clinical analog teduglutide (GLP-2-T) operate through mechanisms that are fundamentally different from acid suppression. Understanding this distinction is central to interpreting peptide research and omeprazole co-administration scenarios.

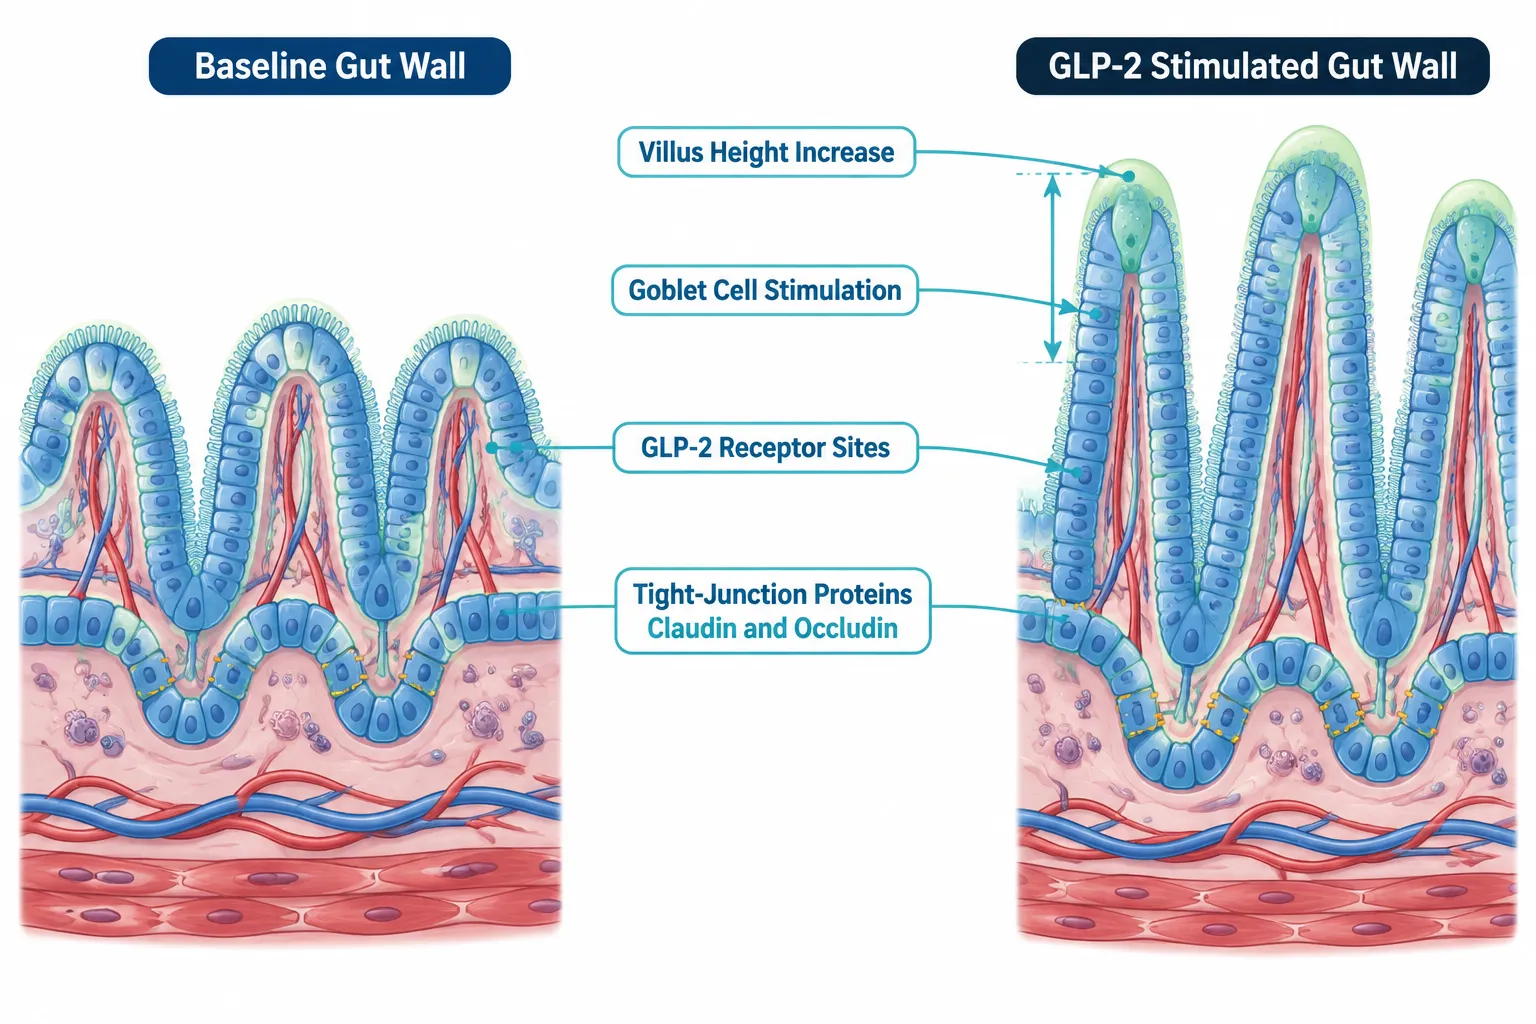
How GLP-2 remodels the intestinal mucosa:

  • Directly stimulates goblet cells to increase mucus production
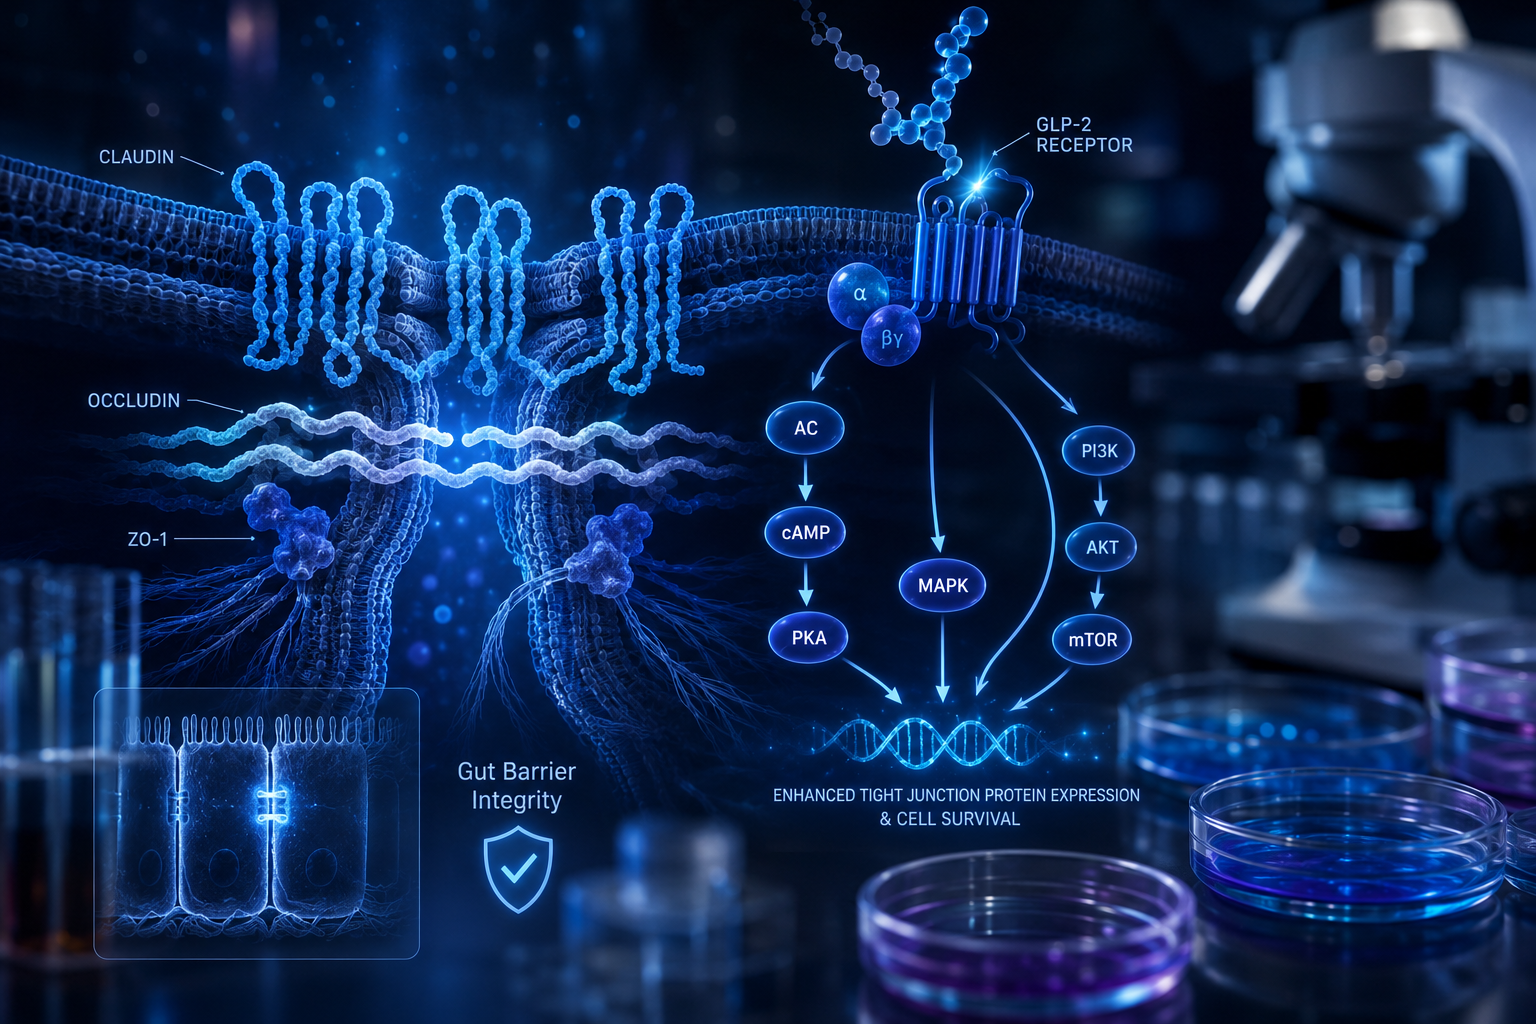
  • Upregulates tight-junction proteins claudin and occludin, strengthening the epithelial barrier
  • Promotes enterocyte proliferation, producing measurable increases in villus height
  • Supports crypt cell survival and reduces apoptosis along the intestinal lining

Compared to the modest barrier improvements seen with PPIs, GLP-2 and GLP-2-T produce substantially larger gains in villus height and barrier function. Longitudinal data from 2025 link GLP-2-T therapy to improved barrier integrity and more favorable microbiota profiles, a meaningful contrast to the microbiota diversity losses associated with long-term PPI use.

For researchers exploring GLP-3 peptide variants and related proglucagon-derived compounds, this mechanistic separation is equally relevant. The mucosal effects of GLP-class peptides operate sufficiently downstream of acid secretion that elevated gastric pH from omeprazole does not appear to blunt their activity.

Those working with GLP-3 R peptide formulations should note that the structural similarities across proglucagon-derived peptides make these pharmacokinetic findings broadly applicable to the class.

Pharmacokinetics: Does Omeprazole Interfere With GLP-Peptide Absorption?

This is the practical question most researchers and clinicians ask first. The short answer, supported by pharmacokinetic data, is no, not in any clinically meaningful way.

Randomized pharmacokinetic studies using oral semaglutide as a structural proxy for proglucagon-derived peptides found only a small, non-statistically-significant increase in peptide exposure when omeprazole was co-administered. The AUC ratio was approximately 1.13 and the Cmax ratio approximately 1.16, changes deemed clinically irrelevant, with no dose adjustment required.

Updated guidance for oral semaglutide in 2026 confirms it can be safely combined with omeprazole, with one practical caveat: take the peptide first on an empty stomach and delay omeprazole by at least 30 minutes. This timing protocol protects bioavailability without requiring formulation changes.

Similar findings apply across the GLP class:

Peptide/Drug Omeprazole Interaction Dose Adjustment Needed?
Oral semaglutide Minor AUC increase (~13%) No
Tirzepatide No known PK or PD interaction No
Liraglutide Low-severity rating, no signal No

For labs sourcing research-grade GLP-3 peptides for gut-focused protocols, this data supports including omeprazole-using participants without automatic exclusion, provided PPI status is recorded and stratified in the analysis.

Study Design Implications: Treating PPI Use as a Covariate

Study Design Implications: Treating PPI Use as a Covariate

The convergence of evidence in 2026 points toward a clear methodological standard for future GLP-2 and teduglutide trials: chronic PPI use must be treated as a pre-specified covariate or exclusion criterion.

The rationale is straightforward. PPIs independently affect:

  1. Mucus layer thickness
  2. Tight-junction protein expression
  3. Gut microbiota composition and diversity
  4. Gastric and intestinal cancer risk over time
  5. Glycemic markers, PPIs show modest HbA1c-lowering effects, likely via increased gastrin and downstream incretin activity

That last point is particularly relevant. Meta-analytic data through 2025-2026 suggest PPIs may modestly improve glycemic control in type 2 diabetes, with HbA1c reductions comparable to some incretin-based therapies. This creates a potential mild synergy, not antagonism, when PPIs are combined with GLP-1 receptor agonists or other gut-acting peptides.

For researchers also evaluating mitochondrial or systemic peptides alongside gut endpoints, resources such as the LL-37 versus SS-31 peptide comparison offer useful context on how peptide class affects study variable selection.

Labs sourcing lab-tested peptides for intestinal research should document participant PPI status at enrollment and consider stratified randomization by PPI use to prevent confounding at the analysis stage.

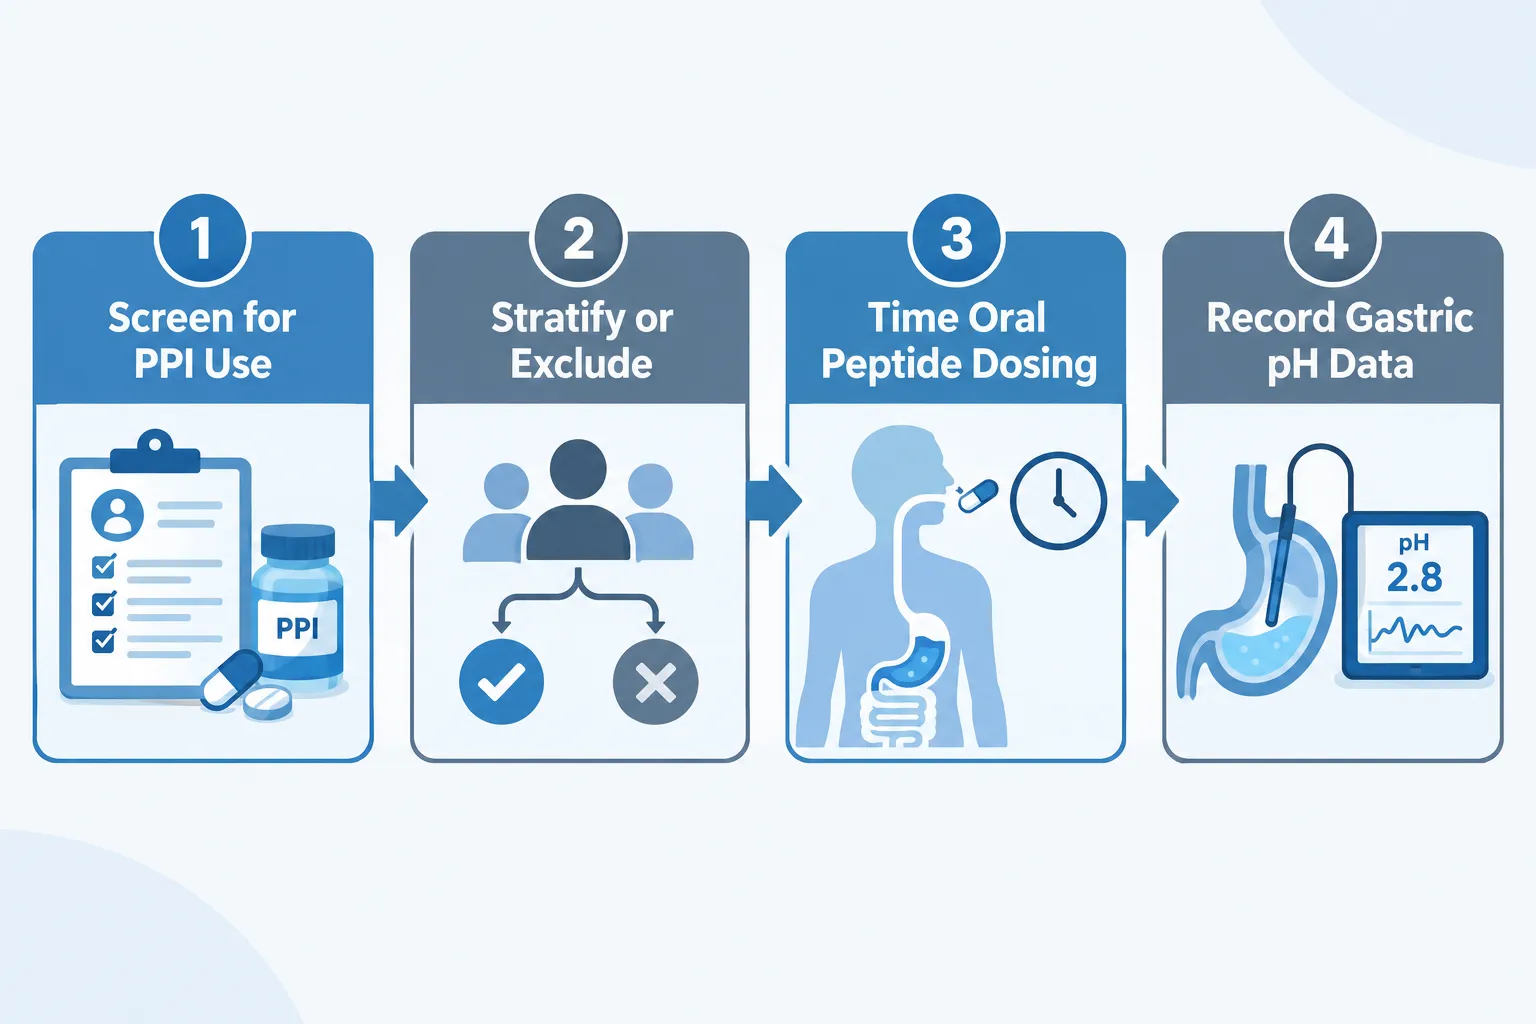
Recommended steps for GLP-2 trial design in 2026:

  1. Screen all participants for current PPI use at baseline
  2. Stratify or exclude chronic PPI users based on study endpoints
  3. For oral peptide arms, standardize the dosing window (empty stomach, 30-minute PPI delay)
  4. Record gastric pH data as a secondary variable where feasible
  5. Pre-specify PPI status as a covariate in the statistical analysis plan

As oral peptide formulations expand, following the template established by oral semaglutide, future GLP-2 analog trials are expected to mirror these protocols, optimizing dosing windows relative to PPIs while leveraging the finding that PPI-induced pH changes alone do not meaningfully suppress peptide exposure.

Conclusion

The relationship between peptide research and omeprazole is more nuanced than a simple drug interaction. Omeprazole does not meaningfully block GLP-2 or GLP-1 class peptide activity at the pharmacokinetic level, but it does independently alter the gut environment in ways that directly overlap with mucosal endpoints these peptides are designed to affect.

Actionable next steps for researchers and study designers:

  • Always document and stratify PPI use in gut-focused peptide protocols, do not treat it as background noise
  • Apply the 30-minute empty-stomach dosing rule for any oral peptide formulation when participants are on PPIs
  • Treat long-term PPI use as a potential confounder for microbiota, barrier integrity, and glycemic endpoints
  • Review updated 2026 guidance for oral GLP-class peptides before finalizing co-administration protocols
  • Consider pre-specifying PPI status as an exclusion criterion or stratification variable in GLP-2-T trials targeting villus height and tight-junction outcomes

Getting this variable right is not a minor methodological detail, it is the difference between clean data and results that cannot be replicated.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptide-research-and-omeprazole-what-acid-suppressing-drugs-mean-for-glp-2-and-g.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:05:452026-09-14 13:05:45Peptide Research and Omeprazole: What Acid-Suppressing Drugs Mean for GLP-2 and Gut-Focused Studies

Tag Archive for: glp-2

GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications

GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications

July 23, 2026/0 Comments/by Pure Tested

Three peptides share the same family name yet serve completely different roles in the body, a distinction that matters enormously for researchers navigating the fast-moving field of metabolic science. Understanding GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications is not just a matter of nomenclature. It shapes how research protocols are designed, which receptor pathways are targeted, and what therapeutic outcomes investigators are pursuing in 2026.

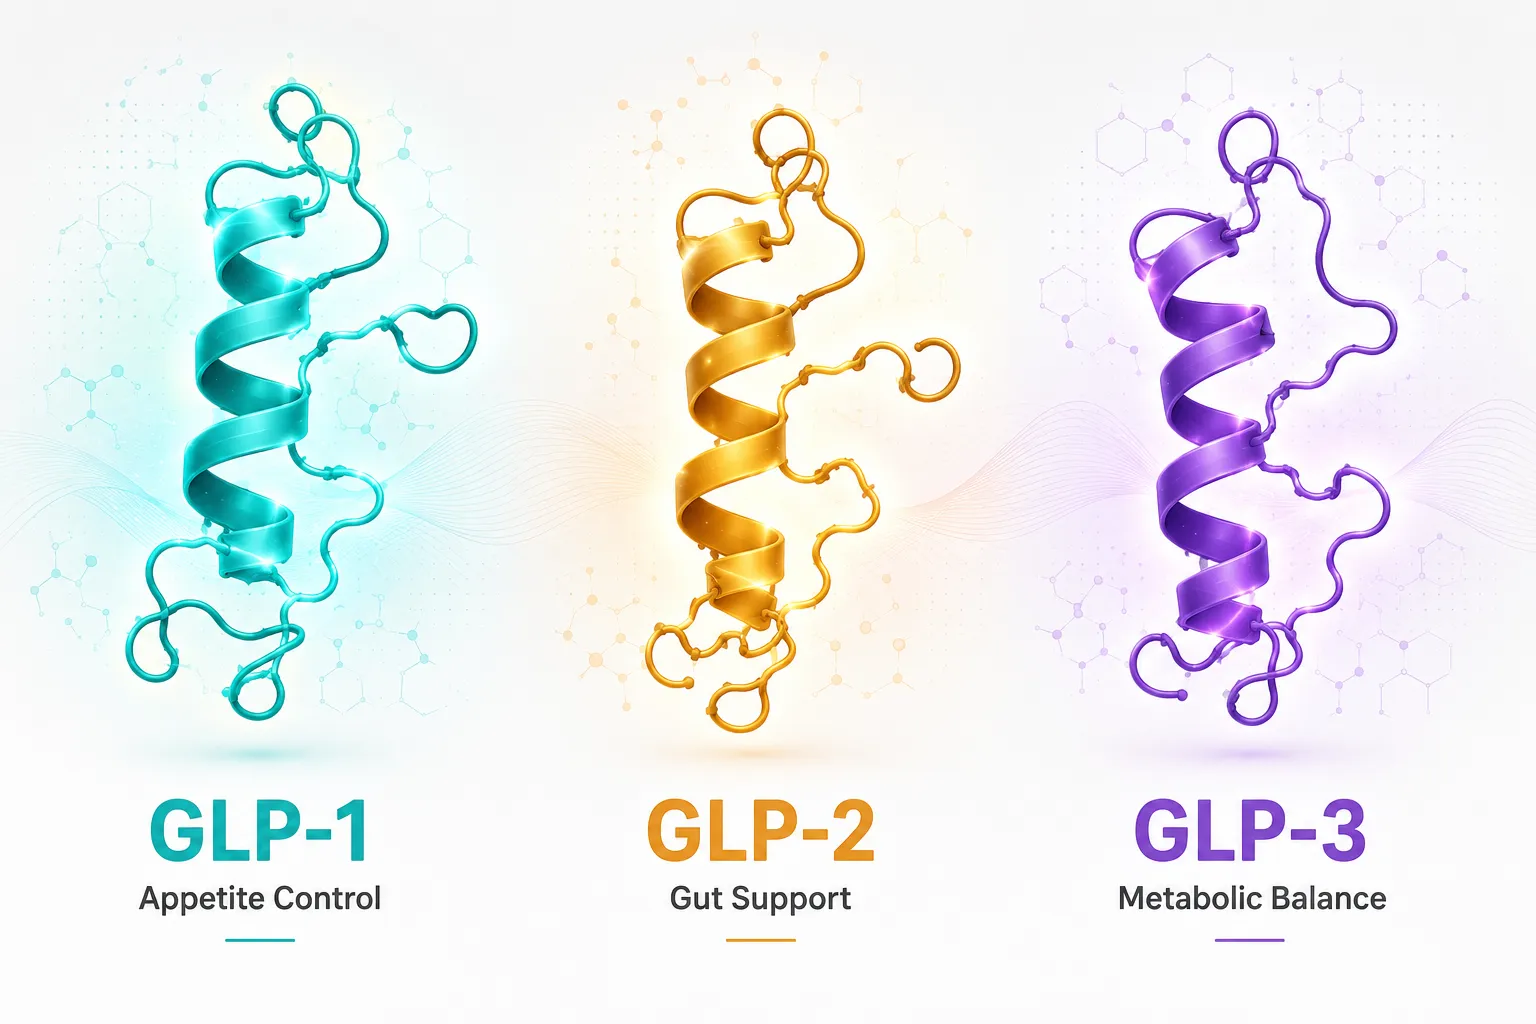
Bright editorial infographic-style landscape (): Three distinct glowing peptide ribbon structures side by side — one labeled

Key Takeaways

  • GLP-1, GLP-2, and GLP-3 are not interchangeable terms, each refers to a distinct biological entity or research concept with unique mechanisms.
  • GLP-1 is a well-characterized gut hormone central to insulin regulation and appetite control, with approved clinical applications.
  • GLP-2 is produced alongside GLP-1 but focuses on intestinal growth and gut integrity rather than metabolic weight regulation.
  • "GLP-3" is an informal nickname for retatrutide, a triple agonist compound targeting GLP-1, GIP, and glucagon receptors simultaneously.
  • Researchers exploring incretin-based peptides should understand receptor specificity before designing or sourcing compounds for study.

Understanding the GLP Peptide Family

The glucagon-like peptides (GLPs) originate from the same precursor protein, proglucagon, which is processed differently depending on the tissue. In the gut, intestinal L-cells cleave proglucagon to produce both GLP-1 and GLP-2. Despite this shared origin, the two peptides bind to entirely different receptors and produce distinct physiological effects.

GLP-1 is released after food intake and triggers a cascade of metabolic responses: it stimulates insulin secretion from the pancreas, suppresses glucagon release, slows gastric emptying, and signals satiety to the brain. These properties made GLP-1 receptor agonists like semaglutide, sold under brand names Ozempic and Wegovy, among the most discussed compounds in modern medicine for type 2 diabetes and obesity management.

GLP-2, released at the same time as GLP-1, acts primarily on the intestinal lining. Its main functions include promoting intestinal cell growth, enhancing nutrient absorption, and maintaining the structural integrity of the gut barrier. GLP-2 does not play a meaningful role in weight regulation. Its clinical relevance is centered on gastrointestinal disorders, particularly short bowel syndrome, where teduglutide (brand name Gattex) is the FDA-approved GLP-2 analog.

Peptide Primary Source Main Target Key Research Area
GLP-1 Intestinal L-cells Pancreas, Brain Metabolic disease, obesity
GLP-2 Intestinal L-cells Intestinal lining Gut health, nutrient absorption
GLP-3 (informal) Synthetic / investigational GLP-1, GIP, Glucagon receptors Obesity, metabolic disorders

Researchers exploring metabolic peptides may also find value in reviewing MOTS-c and metabolic flexibility research themes, which offer complementary insights into mitochondrial and energy regulation pathways.

What Is GLP-3 and Why the Naming Confusion

The term "GLP-3" does not refer to a naturally occurring hormone. It is an informal label, not a recognized scientific classification, that has been applied to retatrutide, an investigational compound currently in clinical trials. Dr. Absalon Gutierrez, an endocrinologist at UTHealth Houston, has explicitly noted that "GLP-3" is sometimes inaccurately used to describe triple hormone receptor agonists rather than a distinct peptide class.

Retatrutide is a triple agonist, meaning it simultaneously activates three receptors:

  • GLP-1 receptor, drives insulin secretion and appetite suppression
  • GIP (glucose-dependent insulinotropic polypeptide) receptor, enhances insulin response and may support fat metabolism
  • Glucagon receptor, increases energy expenditure

This triple receptor activation represents a significant step beyond single agonists like semaglutide and dual agonists like tirzepatide (which targets GLP-1 and GIP). Each additional receptor engagement is associated with incremental metabolic benefits, particularly in the areas of weight reduction and glucose control.

For a deeper look at retatrutide's research profile, the GLP-3 retatrutide incretin research themes page provides a useful overview of current investigational directions.

Preliminary clinical trial data for retatrutide suggests that triple agonism may produce greater weight loss outcomes than either single or dual receptor approaches. However, retatrutide is not yet FDA-approved, and ongoing trials continue to assess its long-term safety and efficacy profile.

What Is GLP-3 and Why the Naming Confusion

Research Applications Across GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications

Understanding the distinct roles of each peptide directly informs how researchers design studies and select compounds. Here is a breakdown of current research applications by peptide type.

GLP-1 Research Applications

  • Insulin secretion dynamics and beta-cell function studies
  • Appetite regulation and central nervous system signaling
  • Cardiovascular risk reduction in metabolic disease models
  • Combination peptide protocols examining synergistic effects

Researchers working with growth hormone-related peptides may also find relevant context in tesa peptide research, particularly where visceral fat reduction and metabolic outcomes overlap with GLP-1 mechanisms.

GLP-2 Research Applications

  • Intestinal mucosal repair and gut barrier function
  • Short bowel syndrome and malabsorption models
  • Nutrient transport and absorption efficiency studies
  • Inflammatory bowel disease-adjacent research

GLP-3 (Retatrutide) Research Applications

  • Triple receptor agonism and energy expenditure modeling
  • Comparative efficacy studies against single and dual agonists
  • Obesity pharmacology and body composition research
  • Metabolic syndrome intervention protocols

For researchers building broader incretin-focused protocols, the GLP-3 retatrutide compound page offers sourcing and documentation resources. Additionally, those interested in how newer triple agonist compounds fit into the evolving peptide landscape can review GLP-3: the newest GLP-1 triple agonist for a broader context.

Key distinction: GLP-1 and GLP-2 are endogenous hormones with well-established physiological roles. GLP-3 is a colloquial term for a synthetic investigational compound with a fundamentally different mechanism of action.

Researchers looking for complementary peptide compounds with documented quality standards should also consult the BPC-157 core peptides research guide as a reference for documentation-first sourcing practices.

GLP-3 (Retatrutide) Research Applications

Conclusion

The distinctions within GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications are foundational for any serious researcher working in metabolic, gastrointestinal, or obesity-related science. GLP-1 governs insulin and appetite signaling. GLP-2 supports gut health and nutrient absorption. And GLP-3, properly understood as retatrutide, represents an emerging class of triple agonist compounds that may redefine how metabolic disorders are studied and treated.

Actionable next steps for researchers:

  1. Clarify which receptor pathway is relevant to the study objective before selecting a compound.
  2. Review current clinical trial data on retatrutide to understand where triple agonism stands in the research pipeline.
  3. Source compounds only from suppliers that provide verified certificates of analysis and quality testing documentation.
  4. Cross-reference GLP-based protocols with complementary peptide research, including growth hormone axis and gut-repair compounds, for a complete metabolic picture.

Staying precise about peptide classification is not just good science, it is the foundation of reproducible, credible research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/glp-1-vs-glp-3-vs-glp-2-peptide-classification-and-research-applications.webp 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-23 13:06:472026-07-27 13:32:10GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family

GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family

June 28, 2026/0 Comments/by Pure Tested

The term "GLP-3" now appears in clinical trial press releases, investor calls, and research databases — yet no such peptide exists in standard biochemistry textbooks. That naming gap reveals something important: the glucagon-like peptide family is evolving faster than its own vocabulary. This guide to GLP-3, GLP-1, and GLP-2 explained as a peptide family cuts through the marketing language to focus on mechanism, receptor biology, and what the evidence actually shows.

Key Takeaways

  • GLP-1 and GLP-2 are both derived from the same precursor protein, proglucagon, through tissue-specific processing.
  • GLP-1 targets the GLP-1 receptor to regulate insulin secretion and appetite; GLP-2 targets a separate receptor to support intestinal growth and repair.
  • "GLP-3" is an informal nickname for retatrutide, a triple agonist hitting GLP-1, GIP, and glucagon receptors — not a distinct endogenous peptide.
  • Multiple next-generation agents in 2026 are blurring receptor boundaries, making precise terminology more important than ever.
  • Researchers should distinguish receptor pharmacology from peptide taxonomy to avoid conflating mechanism with marketing.

GLP-1, GLP-2, and GLP-3 peptide family molecular overview

The Proglucagon Origin: Where GLP-1 and GLP-2 Begin

Understanding GLP-3, GLP-1, and GLP-2 explained as a peptide family starts with a single precursor: proglucagon. This 160-amino-acid protein is encoded by the GCG gene and processed differently depending on the tissue.

Tissue-specific cleavage produces distinct peptides:

Tissue Primary Products
Pancreatic alpha cells Glucagon, glicentin-related peptide
Intestinal L-cells GLP-1, GLP-2, oxyntomodulin
Brain neurons GLP-1, glicentin

This differential processing is controlled by prohormone convertases — PC2 in the pancreas and PC1/3 in the gut and brain. The result is that GLP-1 and GLP-2 are co-secreted from intestinal L-cells in a roughly 1:1 molar ratio following nutrient ingestion.

GLP-1 (glucagon-like peptide-1) is a 30-amino-acid incretin hormone. It binds the GLP-1 receptor (GLP-1R), a class B G-protein-coupled receptor expressed in pancreatic beta cells, the vagus nerve, the hypothalamus, and the heart. Activation drives glucose-dependent insulin secretion, suppresses glucagon, slows gastric emptying, and reduces appetite. Its plasma half-life is under two minutes due to rapid degradation by DPP-4 enzyme.

GLP-2 (glucagon-like peptide-2) is a 33-amino-acid peptide that binds its own distinct receptor, GLP-2R, expressed primarily in intestinal enteroendocrine cells, submucosal neurons, and the hypothalamus. Its core functions center on intestinal epithelial growth, barrier integrity, and nutrient absorption — not glucose regulation. Teduglutide (Gattex/Revestive), a GLP-2 analog, is the only approved agent in this class and generates over $800 million annually. As of 2026, at least six novel GLP-2 analog programs are in active clinical development targeting short bowel syndrome, Crohn's disease, and gut barrier dysfunction. Researchers exploring GLP-1 incretin research themes will find the GLP-2 pathway a compelling parallel.

"GLP-1 and GLP-2 are not interchangeable — they share a precursor but act on entirely different receptor systems with non-overlapping physiological roles."


What "GLP-3" Actually Means: Receptor Taxonomy vs. Peptide Naming

Researcher comparing GLP peptide vials and clinical trial data

The phrase "GLP-3" does not describe a third endogenous glucagon-like peptide. It is an informal shorthand for retatrutide, a synthetic triple agonist developed by Eli Lilly that simultaneously targets three receptors: GLP-1R, GIP receptor (GIPR), and glucagon receptor (GCGR). The "3" refers to the number of receptor targets, not a peptide sequence.

This distinction matters enormously for researchers. Calling retatrutide "GLP-3" is pharmacologically imprecise. The correct terminology is triple receptor agonist or GLP-1/GIP/glucagon tri-agonist. Retatrutide is not FDA-approved as of 2026 and remains available only through clinical trials. Phase 3 data have shown up to 28.7% weight loss, with approval anticipated no earlier than 2027. For more on this compound's research profile, see the dedicated retatrutide and GLP-3 research overview.

Why does the naming confusion persist?

  • Dual agonists like tirzepatide (GLP-1/GIP) were informally called "GLP-2" by some media outlets before that term was corrected.
  • The pharmaceutical pipeline moves faster than regulatory taxonomy.
  • Marketing teams favor simple numerical progressions.

Researchers should also note the generational differences across GLP-1 drug classes to contextualize where triple agonists sit in the therapeutic timeline.


The 2026 Pipeline: Next-Generation Agents Across the GLP Family

Next-generation GLP peptide pipeline timeline and weight-loss data chart

The peptide family landscape in 2026 is defined by receptor combination strategies rather than single-target approaches. Key agents include:

Orforglipron (Foundayo) — Eli Lilly
A once-daily oral GLP-1 receptor agonist. In the ACHIEVE-3 trial, the 17.2 mg dose produced 57.1% greater relative A1C reduction and 73.6% greater relative weight loss compared to oral semaglutide 14 mg. Lilly plans FDA submission by end of Q2 2026.

PF-08653944 — Pfizer
An ultra-long-acting injectable GLP-1 RA achieving 12.3% mean placebo-adjusted weight loss at 28 weeks in the VESPER-3 Phase 2b study, with weight loss continuing after transitioning from weekly to monthly dosing. Ten Phase 3 trials are anticipated in 2026.

Amycretin — Novo Nordisk
A single molecule activating both amylin and GLP-1 receptors, showing 22% weight loss in 36 weeks in Phase 1b/2a trials. Both oral and injectable formulations advance to Phase 3 in 2026.

Survodutide — Boehringer Ingelheim
A dual glucagon/GLP-1 agonist showing 18.7% weight loss at 46 weeks in Phase 2, with 62% of MASH patients achieving disease resolution. Phase 3 trials span 14 countries.

Researchers interested in the broader metabolic peptide landscape can explore metabolic modulation research lines and GIP receptor biology for mechanistic context. Those studying adjacent metabolic compounds may also find value in reviewing AOD9604 metabolic research and SLU-PP-332 metabolic research as comparative reference points.


Conclusion

The GLP peptide family is one of the most productive areas in current biomedical research, but imprecise language creates real confusion. GLP-1 and GLP-2 are endogenous peptides with distinct receptors and non-overlapping functions — both derived from proglucagon but acting on entirely separate physiological systems. "GLP-3" is not a peptide; it is a colloquial label for a triple-receptor agonist strategy.

Actionable next steps for researchers:

  • Anchor all literature searches to receptor nomenclature (GLP-1R, GLP-2R, GIPR, GCGR) rather than informal drug nicknames.
  • Track the orforglipron and retatrutide Phase 3 readouts expected in 2026-2027 as benchmark data for receptor combination strategies.
  • Distinguish between endogenous peptide biology and synthetic analog pharmacology when designing assay protocols.
  • Review the GLP-1 peptide product research library for current research-grade compound availability.

Precise taxonomy is not pedantry — it is the foundation of reproducible science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GLP-3-GLP-1-and-GLP-2-Explained-A-Researchers-Guide-to-the-Peptide-Family.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-28 13:27:522026-07-20 15:01:58GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family
GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family

GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family

June 28, 2026/0 Comments/by Pure Tested

The term "GLP-3" now appears in clinical trial press releases, investor calls, and research databases — yet no such peptide exists in standard biochemistry textbooks. That naming gap reveals something important: the glucagon-like peptide family is evolving faster than its own vocabulary. This guide to GLP-3, GLP-1, and GLP-2 explained as a peptide family cuts through the marketing language to focus on mechanism, receptor biology, and what the evidence actually shows.

Key Takeaways

  • GLP-1 and GLP-2 are both derived from the same precursor protein, proglucagon, through tissue-specific processing.
  • GLP-1 targets the GLP-1 receptor to regulate insulin secretion and appetite; GLP-2 targets a separate receptor to support intestinal growth and repair.
  • "GLP-3" is an informal nickname for retatrutide, a triple agonist hitting GLP-1, GIP, and glucagon receptors — not a distinct endogenous peptide.
  • Multiple next-generation agents in 2026 are blurring receptor boundaries, making precise terminology more important than ever.
  • Researchers should distinguish receptor pharmacology from peptide taxonomy to avoid conflating mechanism with marketing.

GLP-1, GLP-2, and GLP-3 peptide family molecular overview

The Proglucagon Origin: Where GLP-1 and GLP-2 Begin

Understanding GLP-3, GLP-1, and GLP-2 explained as a peptide family starts with a single precursor: proglucagon. This 160-amino-acid protein is encoded by the GCG gene and processed differently depending on the tissue.

Tissue-specific cleavage produces distinct peptides:

Tissue Primary Products
Pancreatic alpha cells Glucagon, glicentin-related peptide
Intestinal L-cells GLP-1, GLP-2, oxyntomodulin
Brain neurons GLP-1, glicentin

This differential processing is controlled by prohormone convertases — PC2 in the pancreas and PC1/3 in the gut and brain. The result is that GLP-1 and GLP-2 are co-secreted from intestinal L-cells in a roughly 1:1 molar ratio following nutrient ingestion.

GLP-1 (glucagon-like peptide-1) is a 30-amino-acid incretin hormone. It binds the GLP-1 receptor (GLP-1R), a class B G-protein-coupled receptor expressed in pancreatic beta cells, the vagus nerve, the hypothalamus, and the heart. Activation drives glucose-dependent insulin secretion, suppresses glucagon, slows gastric emptying, and reduces appetite. Its plasma half-life is under two minutes due to rapid degradation by DPP-4 enzyme.

GLP-2 (glucagon-like peptide-2) is a 33-amino-acid peptide that binds its own distinct receptor, GLP-2R, expressed primarily in intestinal enteroendocrine cells, submucosal neurons, and the hypothalamus. Its core functions center on intestinal epithelial growth, barrier integrity, and nutrient absorption — not glucose regulation. Teduglutide (Gattex/Revestive), a GLP-2 analog, is the only approved agent in this class and generates over $800 million annually. As of 2026, at least six novel GLP-2 analog programs are in active clinical development targeting short bowel syndrome, Crohn's disease, and gut barrier dysfunction. Researchers exploring GLP-1 incretin research themes will find the GLP-2 pathway a compelling parallel.

"GLP-1 and GLP-2 are not interchangeable — they share a precursor but act on entirely different receptor systems with non-overlapping physiological roles."


What "GLP-3" Actually Means: Receptor Taxonomy vs. Peptide Naming

Researcher comparing GLP peptide vials and clinical trial data

The phrase "GLP-3" does not describe a third endogenous glucagon-like peptide. It is an informal shorthand for retatrutide, a synthetic triple agonist developed by Eli Lilly that simultaneously targets three receptors: GLP-1R, GIP receptor (GIPR), and glucagon receptor (GCGR). The "3" refers to the number of receptor targets, not a peptide sequence.

This distinction matters enormously for researchers. Calling retatrutide "GLP-3" is pharmacologically imprecise. The correct terminology is triple receptor agonist or GLP-1/GIP/glucagon tri-agonist. Retatrutide is not FDA-approved as of 2026 and remains available only through clinical trials. Phase 3 data have shown up to 28.7% weight loss, with approval anticipated no earlier than 2027. For more on this compound's research profile, see the dedicated retatrutide and GLP-3 research overview.

Why does the naming confusion persist?

  • Dual agonists like tirzepatide (GLP-1/GIP) were informally called "GLP-2" by some media outlets before that term was corrected.
  • The pharmaceutical pipeline moves faster than regulatory taxonomy.
  • Marketing teams favor simple numerical progressions.

Researchers should also note the generational differences across GLP-1 drug classes to contextualize where triple agonists sit in the therapeutic timeline.


The 2026 Pipeline: Next-Generation Agents Across the GLP Family

Next-generation GLP peptide pipeline timeline and weight-loss data chart

The peptide family landscape in 2026 is defined by receptor combination strategies rather than single-target approaches. Key agents include:

Orforglipron (Foundayo) — Eli Lilly
A once-daily oral GLP-1 receptor agonist. In the ACHIEVE-3 trial, the 17.2 mg dose produced 57.1% greater relative A1C reduction and 73.6% greater relative weight loss compared to oral semaglutide 14 mg. Lilly plans FDA submission by end of Q2 2026.

PF-08653944 — Pfizer
An ultra-long-acting injectable GLP-1 RA achieving 12.3% mean placebo-adjusted weight loss at 28 weeks in the VESPER-3 Phase 2b study, with weight loss continuing after transitioning from weekly to monthly dosing. Ten Phase 3 trials are anticipated in 2026.

Amycretin — Novo Nordisk
A single molecule activating both amylin and GLP-1 receptors, showing 22% weight loss in 36 weeks in Phase 1b/2a trials. Both oral and injectable formulations advance to Phase 3 in 2026.

Survodutide — Boehringer Ingelheim
A dual glucagon/GLP-1 agonist showing 18.7% weight loss at 46 weeks in Phase 2, with 62% of MASH patients achieving disease resolution. Phase 3 trials span 14 countries.

Researchers interested in the broader metabolic peptide landscape can explore metabolic modulation research lines and GIP receptor biology for mechanistic context. Those studying adjacent metabolic compounds may also find value in reviewing AOD9604 metabolic research and SLU-PP-332 metabolic research as comparative reference points.


Conclusion

The GLP peptide family is one of the most productive areas in current biomedical research, but imprecise language creates real confusion. GLP-1 and GLP-2 are endogenous peptides with distinct receptors and non-overlapping functions — both derived from proglucagon but acting on entirely separate physiological systems. "GLP-3" is not a peptide; it is a colloquial label for a triple-receptor agonist strategy.

Actionable next steps for researchers:

  • Anchor all literature searches to receptor nomenclature (GLP-1R, GLP-2R, GIPR, GCGR) rather than informal drug nicknames.
  • Track the orforglipron and retatrutide Phase 3 readouts expected in 2026-2027 as benchmark data for receptor combination strategies.
  • Distinguish between endogenous peptide biology and synthetic analog pharmacology when designing assay protocols.
  • Review the GLP-1 peptide product research library for current research-grade compound availability.

Precise taxonomy is not pedantry — it is the foundation of reproducible science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GLP-3-GLP-1-and-GLP-2-Explained-A-Researchers-Guide-to-the-Peptide-Family.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-28 13:27:522026-07-20 15:01:59GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family
GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family

GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family

June 28, 2026/0 Comments/by Pure Tested

The term "GLP-3" now appears in clinical trial press releases, investor calls, and research databases — yet no such peptide exists in standard biochemistry textbooks. That naming gap reveals something important: the glucagon-like peptide family is evolving faster than its own vocabulary. This guide to GLP-3, GLP-1, and GLP-2 explained as a peptide family cuts through the marketing language to focus on mechanism, receptor biology, and what the evidence actually shows.

Key Takeaways

  • GLP-1 and GLP-2 are both derived from the same precursor protein, proglucagon, through tissue-specific processing.
  • GLP-1 targets the GLP-1 receptor to regulate insulin secretion and appetite; GLP-2 targets a separate receptor to support intestinal growth and repair.
  • "GLP-3" is an informal nickname for retatrutide, a triple agonist hitting GLP-1, GIP, and glucagon receptors — not a distinct endogenous peptide.
  • Multiple next-generation agents in 2026 are blurring receptor boundaries, making precise terminology more important than ever.
  • Researchers should distinguish receptor pharmacology from peptide taxonomy to avoid conflating mechanism with marketing.

GLP-1, GLP-2, and GLP-3 peptide family molecular overview

The Proglucagon Origin: Where GLP-1 and GLP-2 Begin

Understanding GLP-3, GLP-1, and GLP-2 explained as a peptide family starts with a single precursor: proglucagon. This 160-amino-acid protein is encoded by the GCG gene and processed differently depending on the tissue.

Tissue-specific cleavage produces distinct peptides:

Tissue Primary Products
Pancreatic alpha cells Glucagon, glicentin-related peptide
Intestinal L-cells GLP-1, GLP-2, oxyntomodulin
Brain neurons GLP-1, glicentin

This differential processing is controlled by prohormone convertases — PC2 in the pancreas and PC1/3 in the gut and brain. The result is that GLP-1 and GLP-2 are co-secreted from intestinal L-cells in a roughly 1:1 molar ratio following nutrient ingestion.

GLP-1 (glucagon-like peptide-1) is a 30-amino-acid incretin hormone. It binds the GLP-1 receptor (GLP-1R), a class B G-protein-coupled receptor expressed in pancreatic beta cells, the vagus nerve, the hypothalamus, and the heart. Activation drives glucose-dependent insulin secretion, suppresses glucagon, slows gastric emptying, and reduces appetite. Its plasma half-life is under two minutes due to rapid degradation by DPP-4 enzyme.

GLP-2 (glucagon-like peptide-2) is a 33-amino-acid peptide that binds its own distinct receptor, GLP-2R, expressed primarily in intestinal enteroendocrine cells, submucosal neurons, and the hypothalamus. Its core functions center on intestinal epithelial growth, barrier integrity, and nutrient absorption — not glucose regulation. Teduglutide (Gattex/Revestive), a GLP-2 analog, is the only approved agent in this class and generates over $800 million annually. As of 2026, at least six novel GLP-2 analog programs are in active clinical development targeting short bowel syndrome, Crohn's disease, and gut barrier dysfunction. Researchers exploring GLP-1 incretin research themes will find the GLP-2 pathway a compelling parallel.

"GLP-1 and GLP-2 are not interchangeable — they share a precursor but act on entirely different receptor systems with non-overlapping physiological roles."


What "GLP-3" Actually Means: Receptor Taxonomy vs. Peptide Naming

Researcher comparing GLP peptide vials and clinical trial data

The phrase "GLP-3" does not describe a third endogenous glucagon-like peptide. It is an informal shorthand for retatrutide, a synthetic triple agonist developed by Eli Lilly that simultaneously targets three receptors: GLP-1R, GIP receptor (GIPR), and glucagon receptor (GCGR). The "3" refers to the number of receptor targets, not a peptide sequence.

This distinction matters enormously for researchers. Calling retatrutide "GLP-3" is pharmacologically imprecise. The correct terminology is triple receptor agonist or GLP-1/GIP/glucagon tri-agonist. Retatrutide is not FDA-approved as of 2026 and remains available only through clinical trials. Phase 3 data have shown up to 28.7% weight loss, with approval anticipated no earlier than 2027. For more on this compound's research profile, see the dedicated retatrutide and GLP-3 research overview.

Why does the naming confusion persist?

  • Dual agonists like tirzepatide (GLP-1/GIP) were informally called "GLP-2" by some media outlets before that term was corrected.
  • The pharmaceutical pipeline moves faster than regulatory taxonomy.
  • Marketing teams favor simple numerical progressions.

Researchers should also note the generational differences across GLP-1 drug classes to contextualize where triple agonists sit in the therapeutic timeline.


The 2026 Pipeline: Next-Generation Agents Across the GLP Family

Next-generation GLP peptide pipeline timeline and weight-loss data chart

The peptide family landscape in 2026 is defined by receptor combination strategies rather than single-target approaches. Key agents include:

Orforglipron (Foundayo) — Eli Lilly
A once-daily oral GLP-1 receptor agonist. In the ACHIEVE-3 trial, the 17.2 mg dose produced 57.1% greater relative A1C reduction and 73.6% greater relative weight loss compared to oral semaglutide 14 mg. Lilly plans FDA submission by end of Q2 2026.

PF-08653944 — Pfizer
An ultra-long-acting injectable GLP-1 RA achieving 12.3% mean placebo-adjusted weight loss at 28 weeks in the VESPER-3 Phase 2b study, with weight loss continuing after transitioning from weekly to monthly dosing. Ten Phase 3 trials are anticipated in 2026.

Amycretin — Novo Nordisk
A single molecule activating both amylin and GLP-1 receptors, showing 22% weight loss in 36 weeks in Phase 1b/2a trials. Both oral and injectable formulations advance to Phase 3 in 2026.

Survodutide — Boehringer Ingelheim
A dual glucagon/GLP-1 agonist showing 18.7% weight loss at 46 weeks in Phase 2, with 62% of MASH patients achieving disease resolution. Phase 3 trials span 14 countries.

Researchers interested in the broader metabolic peptide landscape can explore metabolic modulation research lines and GIP receptor biology for mechanistic context. Those studying adjacent metabolic compounds may also find value in reviewing AOD9604 metabolic research and SLU-PP-332 metabolic research as comparative reference points.


Conclusion

The GLP peptide family is one of the most productive areas in current biomedical research, but imprecise language creates real confusion. GLP-1 and GLP-2 are endogenous peptides with distinct receptors and non-overlapping functions — both derived from proglucagon but acting on entirely separate physiological systems. "GLP-3" is not a peptide; it is a colloquial label for a triple-receptor agonist strategy.

Actionable next steps for researchers:

  • Anchor all literature searches to receptor nomenclature (GLP-1R, GLP-2R, GIPR, GCGR) rather than informal drug nicknames.
  • Track the orforglipron and retatrutide Phase 3 readouts expected in 2026-2027 as benchmark data for receptor combination strategies.
  • Distinguish between endogenous peptide biology and synthetic analog pharmacology when designing assay protocols.
  • Review the GLP-1 peptide product research library for current research-grade compound availability.

Precise taxonomy is not pedantry — it is the foundation of reproducible science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GLP-3-GLP-1-and-GLP-2-Explained-A-Researchers-Guide-to-the-Peptide-Family.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-28 13:27:512026-07-20 15:01:59GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family
GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family

GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family

June 28, 2026/0 Comments/by Pure Tested

The term "GLP-3" now appears in clinical trial press releases, investor calls, and research databases — yet no such peptide exists in standard biochemistry textbooks. That naming gap reveals something important: the glucagon-like peptide family is evolving faster than its own vocabulary. This guide to GLP-3, GLP-1, and GLP-2 explained as a peptide family cuts through the marketing language to focus on mechanism, receptor biology, and what the evidence actually shows.

Key Takeaways

  • GLP-1 and GLP-2 are both derived from the same precursor protein, proglucagon, through tissue-specific processing.
  • GLP-1 targets the GLP-1 receptor to regulate insulin secretion and appetite; GLP-2 targets a separate receptor to support intestinal growth and repair.
  • "GLP-3" is an informal nickname for retatrutide, a triple agonist hitting GLP-1, GIP, and glucagon receptors — not a distinct endogenous peptide.
  • Multiple next-generation agents in 2026 are blurring receptor boundaries, making precise terminology more important than ever.
  • Researchers should distinguish receptor pharmacology from peptide taxonomy to avoid conflating mechanism with marketing.

GLP-1, GLP-2, and GLP-3 peptide family molecular overview

The Proglucagon Origin: Where GLP-1 and GLP-2 Begin

Understanding GLP-3, GLP-1, and GLP-2 explained as a peptide family starts with a single precursor: proglucagon. This 160-amino-acid protein is encoded by the GCG gene and processed differently depending on the tissue.

Tissue-specific cleavage produces distinct peptides:

Tissue Primary Products
Pancreatic alpha cells Glucagon, glicentin-related peptide
Intestinal L-cells GLP-1, GLP-2, oxyntomodulin
Brain neurons GLP-1, glicentin

This differential processing is controlled by prohormone convertases — PC2 in the pancreas and PC1/3 in the gut and brain. The result is that GLP-1 and GLP-2 are co-secreted from intestinal L-cells in a roughly 1:1 molar ratio following nutrient ingestion.

GLP-1 (glucagon-like peptide-1) is a 30-amino-acid incretin hormone. It binds the GLP-1 receptor (GLP-1R), a class B G-protein-coupled receptor expressed in pancreatic beta cells, the vagus nerve, the hypothalamus, and the heart. Activation drives glucose-dependent insulin secretion, suppresses glucagon, slows gastric emptying, and reduces appetite. Its plasma half-life is under two minutes due to rapid degradation by DPP-4 enzyme.

GLP-2 (glucagon-like peptide-2) is a 33-amino-acid peptide that binds its own distinct receptor, GLP-2R, expressed primarily in intestinal enteroendocrine cells, submucosal neurons, and the hypothalamus. Its core functions center on intestinal epithelial growth, barrier integrity, and nutrient absorption — not glucose regulation. Teduglutide (Gattex/Revestive), a GLP-2 analog, is the only approved agent in this class and generates over $800 million annually. As of 2026, at least six novel GLP-2 analog programs are in active clinical development targeting short bowel syndrome, Crohn's disease, and gut barrier dysfunction. Researchers exploring GLP-1 incretin research themes will find the GLP-2 pathway a compelling parallel.

"GLP-1 and GLP-2 are not interchangeable — they share a precursor but act on entirely different receptor systems with non-overlapping physiological roles."


What "GLP-3" Actually Means: Receptor Taxonomy vs. Peptide Naming

Researcher comparing GLP peptide vials and clinical trial data

The phrase "GLP-3" does not describe a third endogenous glucagon-like peptide. It is an informal shorthand for retatrutide, a synthetic triple agonist developed by Eli Lilly that simultaneously targets three receptors: GLP-1R, GIP receptor (GIPR), and glucagon receptor (GCGR). The "3" refers to the number of receptor targets, not a peptide sequence.

This distinction matters enormously for researchers. Calling retatrutide "GLP-3" is pharmacologically imprecise. The correct terminology is triple receptor agonist or GLP-1/GIP/glucagon tri-agonist. Retatrutide is not FDA-approved as of 2026 and remains available only through clinical trials. Phase 3 data have shown up to 28.7% weight loss, with approval anticipated no earlier than 2027. For more on this compound's research profile, see the dedicated retatrutide and GLP-3 research overview.

Why does the naming confusion persist?

  • Dual agonists like tirzepatide (GLP-1/GIP) were informally called "GLP-2" by some media outlets before that term was corrected.
  • The pharmaceutical pipeline moves faster than regulatory taxonomy.
  • Marketing teams favor simple numerical progressions.

Researchers should also note the generational differences across GLP-1 drug classes to contextualize where triple agonists sit in the therapeutic timeline.


The 2026 Pipeline: Next-Generation Agents Across the GLP Family

Next-generation GLP peptide pipeline timeline and weight-loss data chart

The peptide family landscape in 2026 is defined by receptor combination strategies rather than single-target approaches. Key agents include:

Orforglipron (Foundayo) — Eli Lilly
A once-daily oral GLP-1 receptor agonist. In the ACHIEVE-3 trial, the 17.2 mg dose produced 57.1% greater relative A1C reduction and 73.6% greater relative weight loss compared to oral semaglutide 14 mg. Lilly plans FDA submission by end of Q2 2026.

PF-08653944 — Pfizer
An ultra-long-acting injectable GLP-1 RA achieving 12.3% mean placebo-adjusted weight loss at 28 weeks in the VESPER-3 Phase 2b study, with weight loss continuing after transitioning from weekly to monthly dosing. Ten Phase 3 trials are anticipated in 2026.

Amycretin — Novo Nordisk
A single molecule activating both amylin and GLP-1 receptors, showing 22% weight loss in 36 weeks in Phase 1b/2a trials. Both oral and injectable formulations advance to Phase 3 in 2026.

Survodutide — Boehringer Ingelheim
A dual glucagon/GLP-1 agonist showing 18.7% weight loss at 46 weeks in Phase 2, with 62% of MASH patients achieving disease resolution. Phase 3 trials span 14 countries.

Researchers interested in the broader metabolic peptide landscape can explore metabolic modulation research lines and GIP receptor biology for mechanistic context. Those studying adjacent metabolic compounds may also find value in reviewing AOD9604 metabolic research and SLU-PP-332 metabolic research as comparative reference points.


Conclusion

The GLP peptide family is one of the most productive areas in current biomedical research, but imprecise language creates real confusion. GLP-1 and GLP-2 are endogenous peptides with distinct receptors and non-overlapping functions — both derived from proglucagon but acting on entirely separate physiological systems. "GLP-3" is not a peptide; it is a colloquial label for a triple-receptor agonist strategy.

Actionable next steps for researchers:

  • Anchor all literature searches to receptor nomenclature (GLP-1R, GLP-2R, GIPR, GCGR) rather than informal drug nicknames.
  • Track the orforglipron and retatrutide Phase 3 readouts expected in 2026-2027 as benchmark data for receptor combination strategies.
  • Distinguish between endogenous peptide biology and synthetic analog pharmacology when designing assay protocols.
  • Review the GLP-1 peptide product research library for current research-grade compound availability.

Precise taxonomy is not pedantry — it is the foundation of reproducible science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GLP-3-GLP-1-and-GLP-2-Explained-A-Researchers-Guide-to-the-Peptide-Family.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-28 13:27:512026-07-20 15:02:00GLP-3, GLP-1, and GLP-2 Explained: A Researcher’s Guide to the Peptide Family
GLP-3 Retatrutide vs. GLP-1 and GLP-2: Understanding Receptor Specificity and Research Models

GLP-3 Retatrutide vs. GLP-1 and GLP-2: Understanding Receptor Specificity and Research Models

June 21, 2026/0 Comments/by Pure Tested

A 39-amino acid peptide achieving 28.7% body weight reduction in preliminary Phase 3 data is not a minor incremental advance — it signals a fundamental shift in how researchers think about metabolic receptor targeting. At the center of this shift is retatrutide, often labeled "GLP-3" in research shorthand, and understanding GLP-3 Retatrutide vs. GLP-1 and GLP-2: Understanding Receptor Specificity and Research Models is now essential for anyone following the metabolic peptide research landscape in 2026.

Key Takeaways

  • Retatrutide simultaneously activates three receptors: GLP-1, GIP, and glucagon — unlike GLP-1 or GLP-2 single-agonist peptides.
  • Its receptor potency profile is uneven by design, with the GIP receptor showing the highest binding affinity.
  • Triple-receptor activation addresses both sides of energy balance: reducing caloric intake and increasing energy expenditure.
  • Retatrutide remains investigational as of 2026, with Phase 3 trials ongoing and FDA filing projected for 2026-2027.
  • Structural modifications including a C20 fatty diacid moiety enable once-weekly dosing through extended half-life.

How Receptor Specificity Defines the GLP-3 Retatrutide vs. GLP-1 and GLP-2 Distinction

How Receptor Specificity Defines the GLP-3 Retatrutide vs. GLP-1 and GLP-2 Distinction

The term "GLP-3" is a colloquial label used in research communities to distinguish retatrutide from earlier incretin-based compounds. Formally, retatrutide is a triple agonist — it binds and activates the GLP-1 receptor, the GIP receptor, and the glucagon receptor. This is categorically different from GLP-1 receptor agonists like semaglutide, which target a single receptor, and from GLP-2, a peptide primarily involved in intestinal growth and repair through its own dedicated receptor.

Understanding the receptor specificity comparison requires looking at potency data:

Receptor EC50 Value Relative Potency vs. Native Peptide
GIP Receptor 0.0643 nM ~8.9x more potent than native GIP
GLP-1 Receptor 0.775 nM ~0.4x potency of native GLP-1
Glucagon Receptor 5.79 nM ~0.3x potency of native glucagon

This asymmetric potency profile is intentional. The GIP receptor is activated most strongly, while glucagon receptor engagement is kept moderate — enough to drive thermogenesis and fat mobilization without triggering hyperglycemia. GLP-1 receptor activation suppresses appetite and enhances insulin secretion, while GLP-2 operates on an entirely separate pathway focused on gut mucosal integrity, making it functionally distinct from retatrutide's mechanism.

For researchers exploring incretin biology, the GLP-3 incretin research themes page provides a useful foundation for understanding how this triple-agonist model differs from classic GLP-1 frameworks.


Downstream Signaling Pathways: Where GLP-3 Retatrutide vs. GLP-1 and GLP-2 Research Models Diverge

Downstream Signaling Pathways: Where GLP-3 Retatrutide vs. GLP-1 and GLP-2 Research Models Diverge

The downstream effects of receptor activation explain why retatrutide produces outcomes that single-agonist peptides cannot replicate. Each receptor pathway contributes a distinct physiological signal:

  • GLP-1 receptor activation: Slows gastric emptying, reduces appetite via central nervous system signaling, and stimulates glucose-dependent insulin release.
  • GIP receptor activation: Enhances insulin secretion, may improve insulin sensitivity, and contributes to adipose tissue regulation.
  • Glucagon receptor activation: Increases hepatic glucose output at low levels, but more critically at therapeutic doses, drives thermogenesis and promotes lipolysis.

GLP-2, by contrast, signals primarily through receptors in the intestinal epithelium, stimulating mucosal growth and nutrient absorption. Its downstream effects are largely confined to the gut, with no meaningful overlap with the metabolic energy-balance pathways that retatrutide engages.

This divergence has significant implications for research model design. Studies examining retatrutide must account for simultaneous multi-receptor crosstalk, whereas GLP-1 or GLP-2 models involve cleaner, more isolated signaling environments. Researchers interested in how GIP receptor dynamics fit into this picture can explore the GIP receptor and its importance for additional context.

Those comparing generational differences in GLP-1 compounds may also find value in reviewing generations of GLP-1 differences to place retatrutide's design within a broader evolutionary framework of incretin drug development.


Clinical Research Outcomes and the Triple-Agonist Advantage

Clinical Research Outcomes and the Triple-Agonist Advantage

The clinical data emerging from retatrutide trials reflects the compounded benefit of triple-receptor engagement. Phase 2 results showed up to 24.2% body weight reduction over 48 weeks. Preliminary Phase 3 data pushes that figure to 28.7% at 68 weeks — a result that exceeds outcomes from both semaglutide and tirzepatide in comparable timeframes.

Structurally, retatrutide is built on a GIP peptide backbone, modified with 2-aminoisobutyric acid (Aib) residues and a C20 fatty diacid moiety. These modifications resist enzymatic degradation and extend the half-life to approximately six days, making once-weekly subcutaneous dosing feasible. Steady-state plasma concentrations are typically reached within four to five weeks of consistent administration.

As of 2026, retatrutide remains investigational. It has not received FDA approval and is available only in research and clinical trial contexts. An FDA filing is projected for 2026-2027 pending Phase 3 completion.

Researchers building multi-pathway metabolic models may also find it useful to examine how other compounds interact with energy regulation. The SLU-PP-332 metabolic modulation research themes page outlines complementary pathways that some researchers study alongside incretin-based models. Similarly, the GLP-1 peptide generational research concepts resource provides sourcing and conceptual context for GLP-1 receptor research.

For those specifically focused on retatrutide as a research compound, the GLP-3 triple agonist research planning page offers catalog navigation and planning guidance.


Conclusion

The comparison of GLP-3 Retatrutide vs. GLP-1 and GLP-2: Understanding Receptor Specificity and Research Models reveals a clear hierarchy of mechanistic complexity. GLP-2 operates in a gut-specific domain. GLP-1 agonists provide meaningful but single-pathway metabolic control. Retatrutide, through its calibrated triple-receptor engagement, addresses energy balance from multiple angles simultaneously — a design that its clinical outcomes appear to validate.

Actionable next steps for researchers:

  • Review published Phase 2 and Phase 3 trial protocols to understand retatrutide's dosing and endpoint design before building research models.
  • Map receptor crosstalk carefully when designing in vitro or preclinical studies involving triple agonists.
  • Compare GIP receptor potency data against GLP-1 receptor data to understand which pathway dominates at different dose levels.
  • Monitor FDA filing updates projected for 2026-2027 to track regulatory trajectory.
  • Consult the GLP-3 newest triple agonist overview for updated research framing as new data emerges.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GLP-3-Retatrutide-vs.-GLP-1-and-GLP-2-Understanding-Receptor-Specificity-and-Research-Models.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-21 13:05:362026-07-20 15:02:37GLP-3 Retatrutide vs. GLP-1 and GLP-2: Understanding Receptor Specificity and Research Models
GLP-2 and GLP-2-Tirzepatide: Research into Intestinal Growth Factors and Gut Barrier Function

GLP-2 and GLP-2-Tirzepatide: Research into Intestinal Growth Factors and Gut Barrier Function

June 20, 2026/0 Comments/by Pure Tested

Short bowel syndrome affects roughly 3 in every million people, yet the peptide hormone at the center of emerging gut repair research — GLP-2 — was only identified in the 1980s. Today, research into GLP-2 and GLP-2-Tirzepatide: Research into Intestinal Growth Factors and Gut Barrier Function is reshaping how scientists understand the intestine as a dynamic, hormonally regulated organ.

Detailed () scientific illustration showing GLP-2 hormone molecules being secreted from enteroendocrine L-cells in the

Key Takeaways

  • GLP-2 is an intestinally derived hormone that drives mucosal growth, barrier repair, and nutrient absorption.
  • Its actions are largely indirect, mediated through IGF-1, EGF, and tight junction protein modulation.
  • Dual-receptor agonists combining GLP-1 and GLP-2 activity (such as dapiglutide) show enhanced barrier protection in preclinical models.
  • Tirzepatide's structural relationship to incretin biology opens new research questions about combined gut-metabolic signaling.
  • Age-related gut decline may be a future target for GLP-2-based interventions.

What Is GLP-2 and Why Does It Matter for Gut Health

Glucagon-like peptide-2 (GLP-2) is a 33-amino acid hormone secreted by enteroendocrine L-cells lining the small and large intestine. It is released in direct response to nutrient intake, making it a key postprandial signal.

Its primary roles include:

  • Stimulating crypt cell proliferation (intestinal growth)
  • Inhibiting apoptosis and proteolysis in mucosal tissue
  • Enhancing nutrient absorption and reducing mucosal permeability
  • Regulating gastric emptying and acid secretion

GLP-2 does not act alone. Its intestinotropic effects are mediated through a network of indirect signals, particularly insulin-like growth factor-1 (IGF-1) and epidermal growth factor (EGF). These downstream mediators drive the crypt cell proliferation that gives GLP-2 its reputation as a potent intestinal growth factor.

Researchers studying related metabolic peptides — including those exploring GLP-1 and incretin research themes — have noted that the GLP family shares structural and functional overlap worth investigating in parallel.


GLP-2 and Gut Barrier Function: The Tight Junction Connection

One of the most clinically significant findings in GLP-2 research involves its effect on the intestinal epithelial barrier. A healthy gut barrier depends on tight junction proteins — including claudin and occludin — that seal gaps between epithelial cells and prevent bacterial translocation.

GLP-2 improves both:

Pathway Mechanism
Transcellular Enhanced nutrient transport across epithelial cells
Paracellular Tight junction protein upregulation via IE-IGF-1R signaling

The intestinal epithelial IGF-1 receptor (IE-IGF-1R) appears central to this process. When GLP-2 binds its receptor on subepithelial cells, it triggers IGF-1 release, which then acts on epithelial IGF-1 receptors to reinforce tight junction integrity.

Research in aged animal models found that GLP-2 administration reversed age-associated declines in mucosal barrier function — a finding with significant implications for longevity-focused gastrointestinal research. This connects naturally to broader work on mitochondrial and longevity research themes where cellular resilience is a shared focus.

GLP-2 also appears to orchestrate gut microbiota interactions, supporting immune homeostasis and reducing inflammatory signaling at the mucosal surface.


GLP-2 and GLP-2-Tirzepatide: Research into Intestinal Growth Factors and Gut Barrier Function — The Dual-Receptor Frontier

GLP-2 and GLP-2-Tirzepatide: Research into Intestinal Growth Factors and Gut Barrier Function — The Dual-Receptor Frontier

Tirzepatide is best known as a dual GIP/GLP-1 receptor agonist with metabolic effects. However, emerging structural pharmacology research is exploring whether tirzepatide's incretin backbone can be modified or combined with GLP-2 activity to create multi-target gut-metabolic agents.

A 2022 study on dapiglutide — a dual GLP-1/GLP-2 receptor agonist — demonstrated measurable improvements in intestinal barrier function in a murine short bowel model. This proof-of-concept supports the hypothesis that combining incretin signaling with GLP-2 intestinotrophic activity could offer additive benefits.

Researchers interested in GLP-3 and retatrutide research are also examining how multi-receptor engagement affects gut architecture beyond glycemic control.

GLP-2 and GLP-2-Tirzepatide: Research into Intestinal Growth Factors and Gut Barrier Function — The Dual-Receptor Frontier

Key research questions currently being explored include:

  • Can tirzepatide-adjacent molecules be engineered to also activate GLP-2 receptors?
  • Does combined GLP-1/GLP-2 signaling reduce intestinal permeability more effectively than either alone?
  • What role does the gut microbiome play in modulating these effects?

For researchers exploring metabolic and body composition peptides, AOD9604 metabolic research and TESA body composition research themes offer relevant comparative frameworks for understanding how gut-derived hormones influence systemic metabolism.


Conclusion

Research into GLP-2 and GLP-2-Tirzepatide: Research into Intestinal Growth Factors and Gut Barrier Function represents one of the most promising frontiers in gastrointestinal biology in 2026. GLP-2 is not simply a growth signal — it is a multi-functional regulator of barrier integrity, immune balance, and nutrient homeostasis.

Actionable next steps for researchers:

  1. Review preclinical models using dual GLP-1/GLP-2 agonists to identify translatable endpoints.
  2. Examine IGF-1 receptor signaling as a measurable biomarker for GLP-2 barrier activity.
  3. Explore synergies between GLP-2 pathways and other gut-protective peptides, including those catalogued in the comprehensive peptide research catalog.
  4. Monitor emerging data on tirzepatide-derived multi-receptor molecules for intestinal applications.

The intersection of incretin pharmacology and intestinal growth factor biology is still early-stage — but the mechanistic groundwork laid by GLP-2 research makes it one of the most compelling areas to watch.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GLP-2-and-GLP-2-Tirzepatide-Research-into-Intestinal-Growth-Factors-and-Gut-Barrier-Function.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-20 13:03:322026-07-20 15:02:40GLP-2 and GLP-2-Tirzepatide: Research into Intestinal Growth Factors and Gut Barrier Function
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top