Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: growth hormone peptides

Electrolytes and Research Peptides: Designing Fluid-Balance Controls for GLP, Growth-Hormone, and Metabolic Studies

Electrolytes and Research Peptides: Designing Fluid-Balance Controls for GLP, Growth-Hormone, and Metabolic Studies

November 9, 2026/0 Comments/in Uncategorized/by

A single unmonitored shift in serum sodium can quietly invalidate blood-pressure readings, skew DEXA-derived body composition, and compress glucose signals enough to blur a treatment effect entirely. For researchers working with GLP-1 receptor agonists, growth-hormone secretagogues, and multi-agonist peptides, that is not a hypothetical. Fluid-balance disturbances are now recognized as an intrinsic feature of these compounds, not incidental side effects. Designing proper controls for electrolytes and research peptides, across GLP, growth-hormone, and metabolic studies, has become a defining quality marker for 2026 trial methodology.

Key Takeaways

  • GLP-1 receptor agonists actively regulate sodium excretion, arginine vasopressin signaling, and fluid intake, making electrolyte monitoring a core safety endpoint, not a secondary one.
  • Sodium, potassium, extracellular volume, and hydration status each distort body-composition, blood-pressure, and metabolic readouts when left uncontrolled.
  • Peptides such as retatrutide, CJC-1295, ipamorelin, and tesa each carry distinct fluid-balance risk profiles that call for tailored monitoring schedules.
  • Integrated control frameworks should baseline-screen for AVP deficiency and CKD, then track copeptin, urine volume, and sodium at pre-specified intervals.
  • Fluid and electrolyte controls should be engineered into the study design from the start, not retrofitted as general safety monitoring.

Why Electrolytes Distort Metabolic and Body-Composition Readouts
Why Electrolytes Distort Metabolic and Body-Composition Readouts

Body weight is not fat mass. That statement matters enormously in peptide research, where multi-kilogram changes on the scale over days can reflect shifts in extracellular water rather than adipose tissue loss. Sodium retention expands plasma volume, inflating body weight and elevating blood pressure independently of any true metabolic change. Potassium depletion alters cardiac excitability and can confound electrocardiographic safety endpoints. Dehydration, conversely, artificially concentrates glucose and creatinine, making metabolic improvement appear greater, or metabolic toxicity appear worse, than it actually is.

How individual electrolytes affect readouts:

Electrolyte / Variable Effect When Elevated Effect When Depleted
Serum sodium Volume expansion, BP rise, weight gain Dilutional hyponatremia, fatigue, confusion
Serum potassium Bradycardia risk, masked insulin effects Glucose dysregulation, cardiac arrhythmia
Extracellular volume DEXA lean-mass overestimate Underestimated fat-free mass
Hydration status Diluted glucose, lower Hb A1c Falsely elevated glucose, creatinine, hematocrit

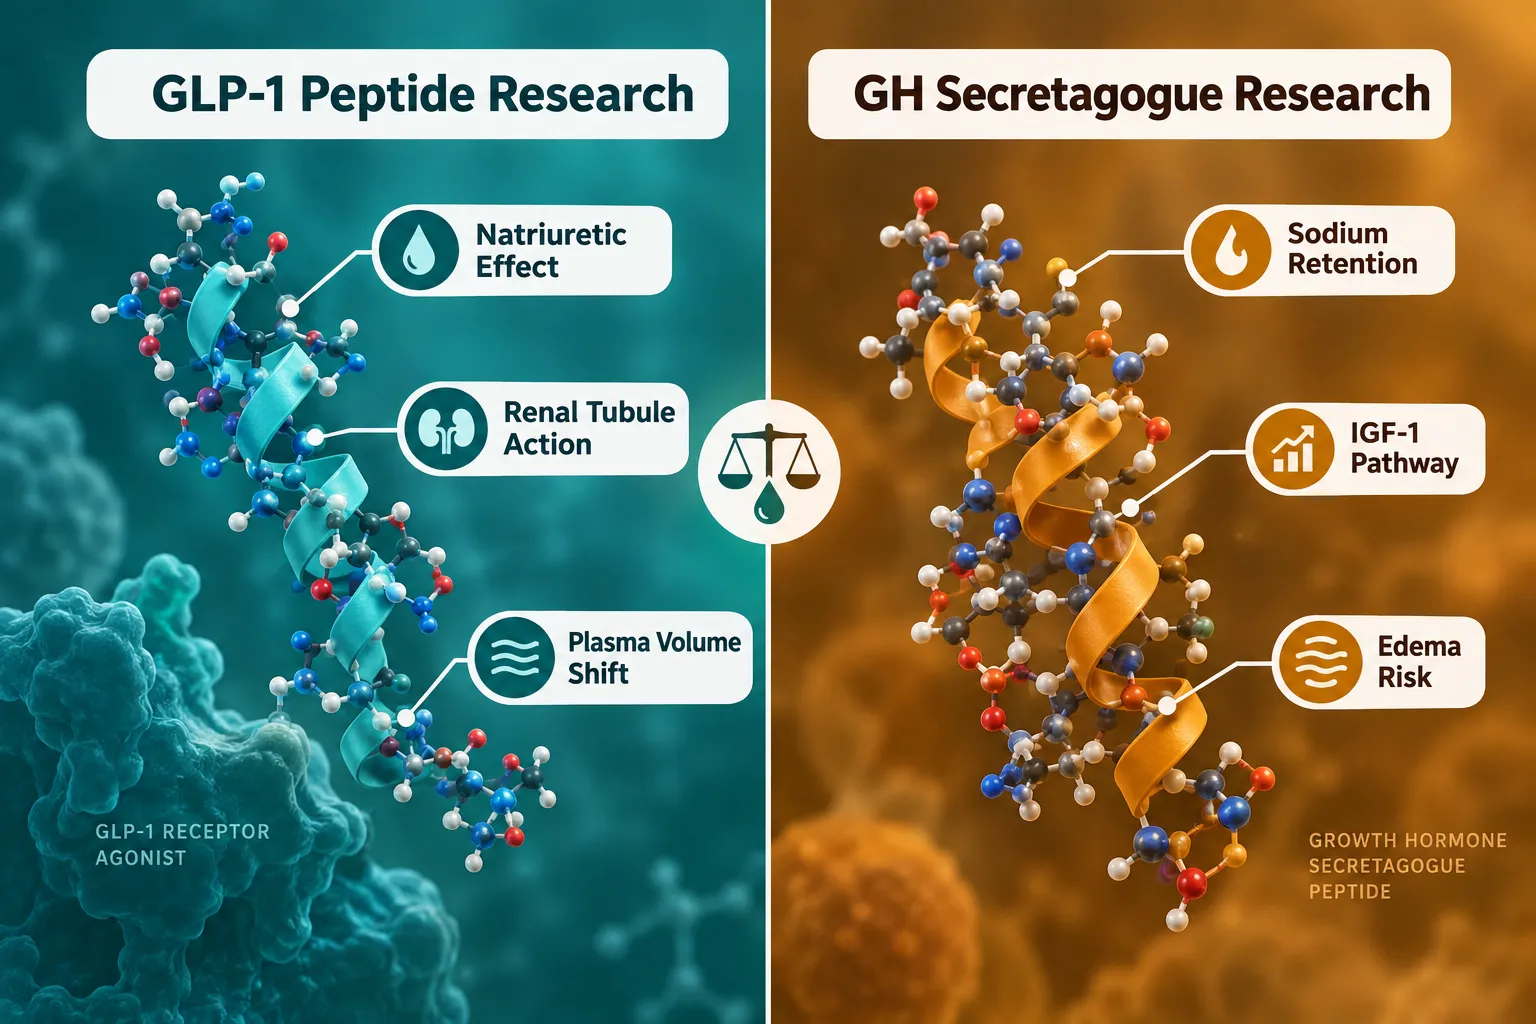
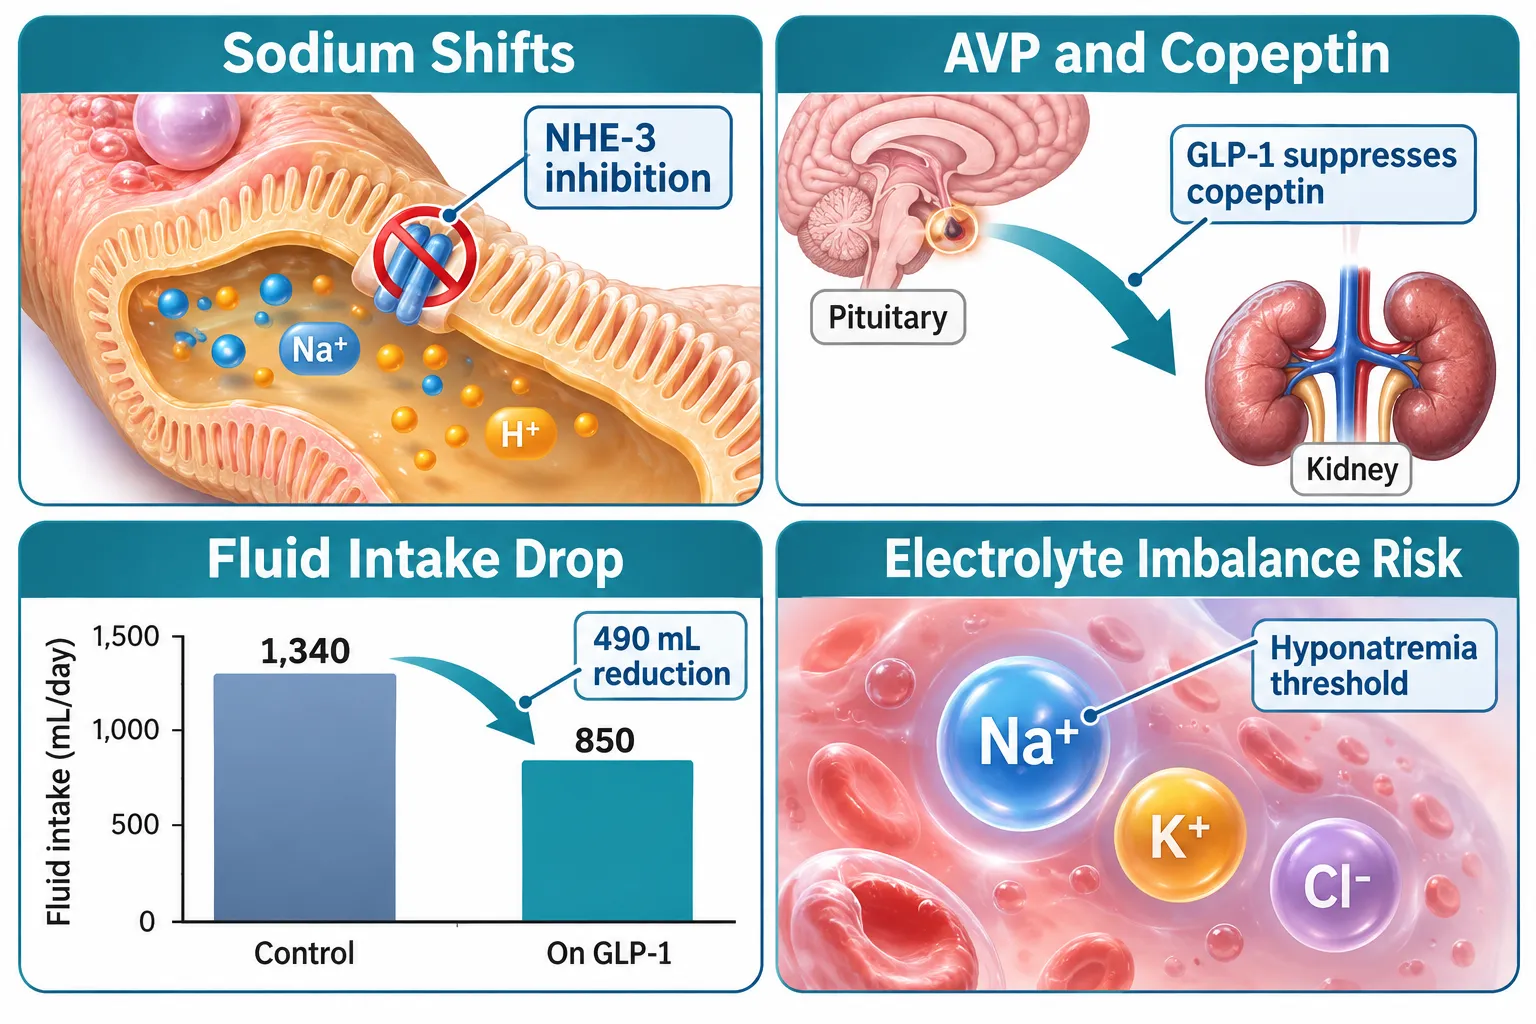
These distortions are especially acute in GLP-1 studies because GLP-1 receptor agonists inhibit proximal tubular sodium-hydrogen exchanger 3 (NHE-3), increasing urinary sodium and water excretion. In a chronic kidney disease context, that natriuresis helps alleviate fluid overload, but in a lean research participant, it can produce rapid shifts in both body weight and blood pressure that are entirely unrelated to energy metabolism. Without proper controls, investigators risk attributing fluid-driven changes to pharmacological efficacy.


Fluid-Balance Profiles of Key Research Peptides

Fluid-Balance Profiles of Key Research Peptides

Electrolytes and research peptides present different fluid-balance challenges depending on the compound class, half-life, and receptor target. Understanding these distinctions is the first step toward designing controls that actually match the biology.

GLP-1 Receptor Agonists and Dual Agonists

Long-acting GLP-1 receptor agonists such as dulaglutide have been shown to reduce total daily fluid intake by approximately 490 mL compared with placebo. In controlled volunteer studies, 24-hour urine output dropped from roughly 1,680 mL to 1,250 mL. This hypodipsic effect works partly through arginine vasopressin (AVP) suppression, tracked via copeptin, and partly through direct renal NHE-3 inhibition.

Short-acting GLP-1 agents primarily drive natriuresis with less impact on thirst. That distinction matters for protocol design: stratify fluid-balance monitoring by agent half-life, not just by receptor class.

For GLP-1 peptide sourcing and generational research concepts, understanding the pharmacokinetic profile of the specific compound in hand is non-negotiable before designing a fluid endpoint.

Dual GLP-1/GIP agonists, including the retatrutide scaffold, add GIP receptor and glucagon receptor activity. This broader agonism can precipitate early hyponatremia in participants with underlying AVP deficiency. Researchers sourcing GLP-3 peptides for sale for multi-agonist comparisons should build in serum sodium checks at weeks one and two of exposure, with pre-specified thresholds for dose reduction.

Key design rule: Any GLP-1 or multi-agonist peptide study that uses blood pressure, body weight, or kidney function as primary outcomes must treat fluid and electrolyte monitoring as co-primary endpoints, not footnotes.

For researchers working with the GLP-3R 10 mg peptide or related analogs, baseline copeptin measurement before first dose provides a critical reference point.

Growth-Hormone Secretagogues: CJC-1295, Ipamorelin, and Tesamorelin

Growth-hormone (GH) secretagogues operate through a different mechanism, but share one important fluid consequence: pharmacologic GH elevation consistently causes sodium and water retention, mild extracellular volume expansion, and in some subjects, peripheral edema. This makes DEXA-derived lean mass gains difficult to interpret without concurrent fluid-balance data.

Control variables specific to GH secretagogue studies:

  • Daily morning body weight under standardized hydration conditions
  • Urinary sodium and creatinine at baseline and every two weeks
  • Blood pressure at each study visit, noting time since last peptide dose
  • Hematocrit as a hemoconcentration marker
  • Self-reported fluid intake log

Tesamorelin, approved for HIV-associated lipodystrophy, has the most extensive safety database among GH-releasing factor analogs. Its effects on visceral adipose tissue are real, but trial-level body-composition readouts can be distorted by the volume-retention signal if sodium and fluid controls are not in place. CJC-1295 combined with ipamorelin produces sustained GH pulses; without fluid monitoring, an apparent lean-mass gain of 1-2 kg in the early weeks may be partly or entirely water.

For reference standards and peptide benchmarking, pairing compound-identity verification with a fluid-balance sub-protocol is now considered best practice.


Designing Integrated Fluid-Balance Controls for Peptide Studies
Designing Integrated Fluid-Balance Controls for Peptide Studies

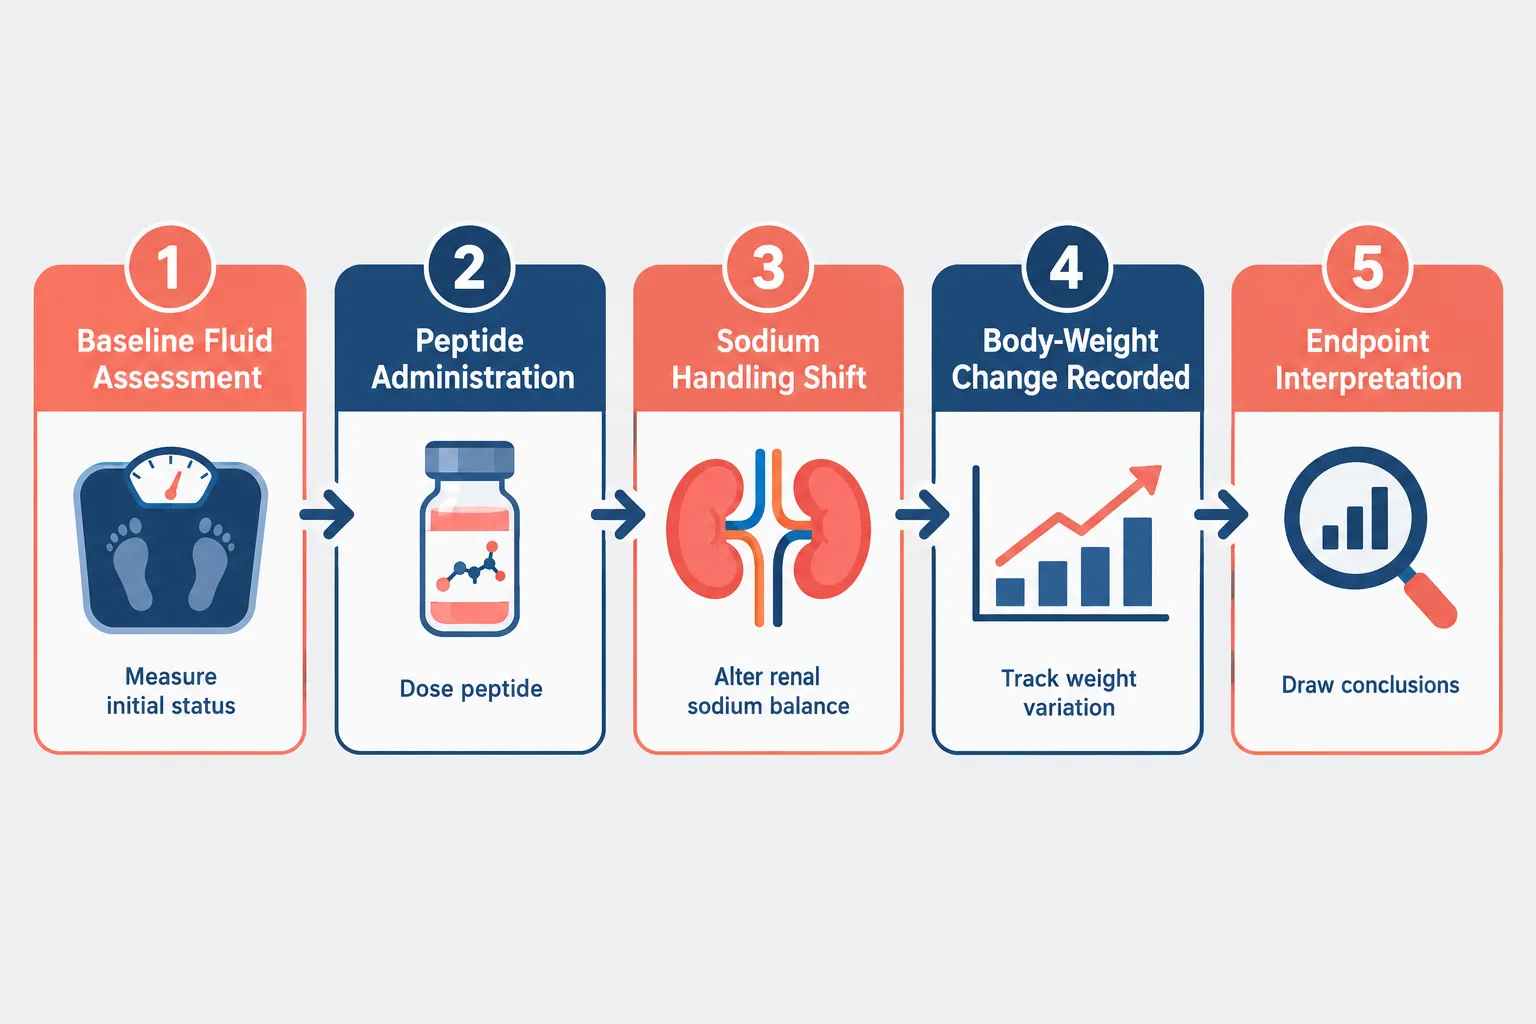
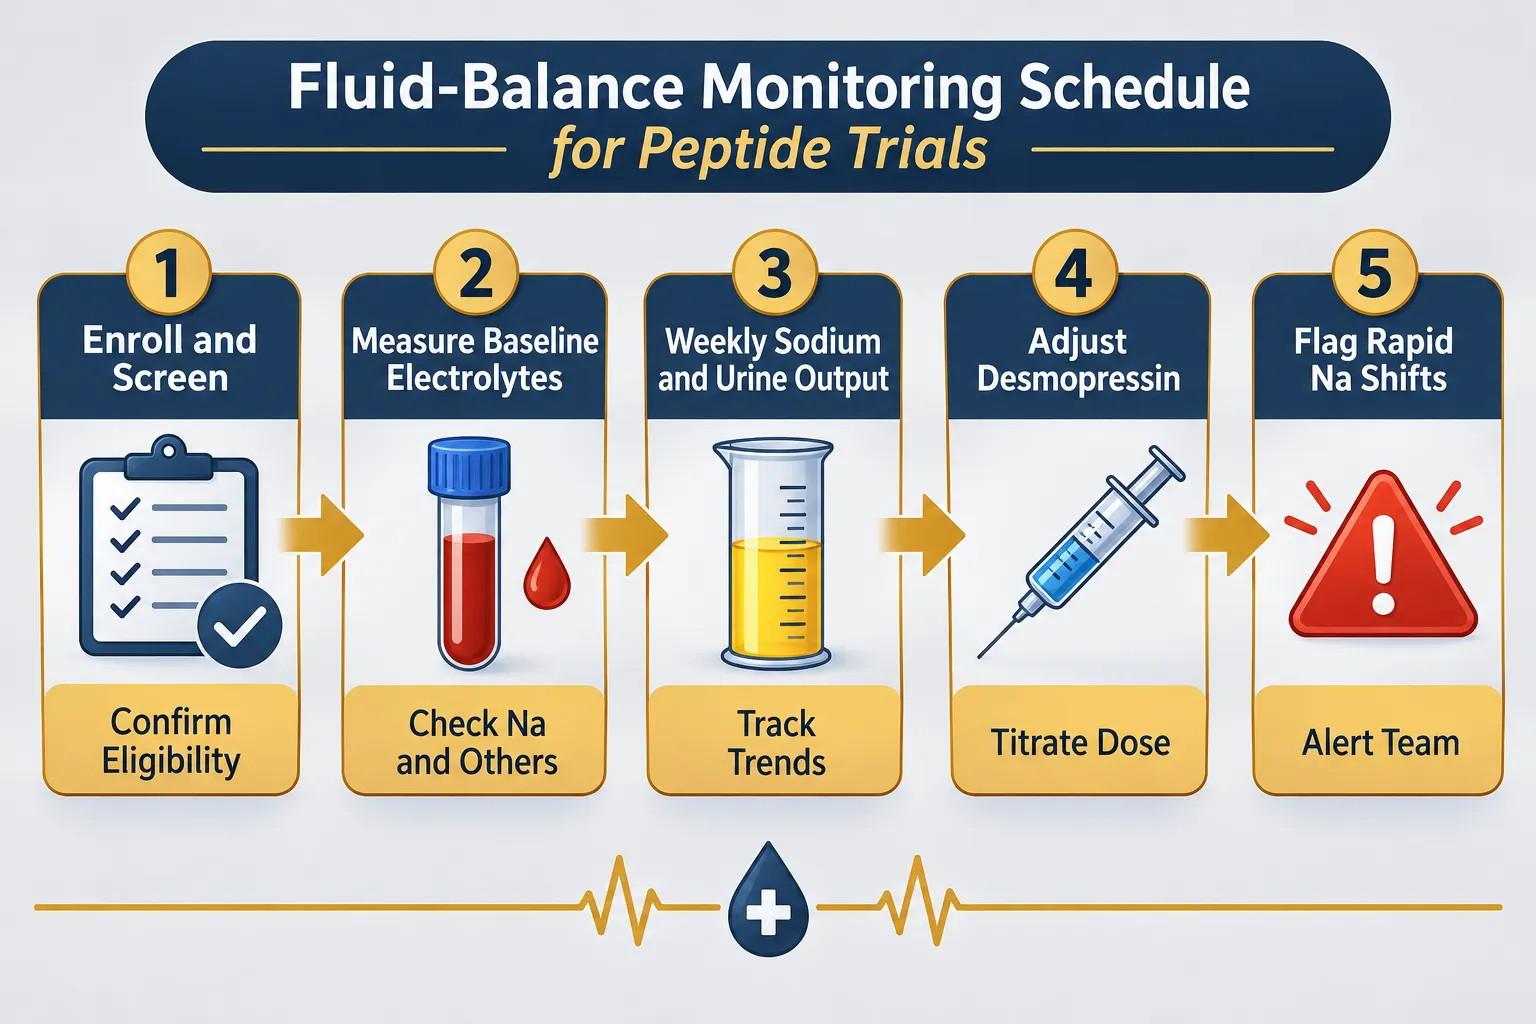
A practical, integrated control framework for electrolytes and research peptides in GLP, growth-hormone, and metabolic studies includes five structured elements drawn from 2024-2026 endocrinology and nephrology consensus:

Step 1, Pre-enrollment screening: Screen all participants for AVP deficiency, CKD stages 3-5, and baseline hyponatremia (sodium below 135 mEq/L). Flag heart failure and concurrent RAAS inhibitor or diuretic use as elevated-risk categories requiring more frequent panels.

Step 2, Baseline biomarker capture: Measure copeptin, serum sodium, potassium, creatinine, and 24-hour urine volume before the first dose. These values anchor all subsequent comparisons.

Step 3, Scheduled interval monitoring: Repeat the basic metabolic panel and copeptin at weeks one, two, four, and eight, more frequently (every three to five days) during the first two weeks in AVP-deficient or CKD participants. Track ad libitum fluid intake and 24-hour urine output as co-primary or key secondary endpoints.

Step 4, Desmopressin and fluid management rules: Cap daily desmopressin doses in AVP-deficient participants and adjust based on urine output data. When GI side effects (nausea, vomiting, diarrhea) emerge, common with GLP-1 agonists, replace fluids with electrolyte-containing solutions rather than plain water to prevent dilutional shifts.

Step 5, Pre-specified stopping rules: Define halt thresholds for rapid sodium change (greater than 10 mEq/L in 24 hours in either direction) and for unexpected oliguria or polyuria. Document these in the protocol before enrollment begins.

For researchers sourcing compounds through curated catalogs, wholesale peptides with verified purity documentation make it easier to rule out impurity-driven fluid effects as a confounding variable.

Studies enrolling participants with high cardiovascular or renal risk, the population most likely to be affected by natriuresis or diuresis, should start at lower peptide doses, shorten the titration interval, and prepare individualized fluid-intake targets in advance. Reviewing GLP peptides for sale with attention to formulation, excipients, and concentration helps avoid osmolarity-related fluid artifacts from the reconstitution vehicle itself.


Conclusion

The most important conceptual shift in peptide research methodology over the past three years is this: GLP-1 and related compounds are salt-and-water hormones as much as metabolic ones. Sodium handling, AVP suppression, renal tubular transport, and urinary volume are not side effects to manage, they are biological outputs to measure. The same logic, applied with appropriate modification for fluid-retention rather than fluid-loss patterns, extends to growth-hormone secretagogues including CJC-1295, ipamorelin, and tesamorelin.

Actionable next steps for researchers in 2026:

  1. Add copeptin, serum sodium, and 24-hour urine volume to the primary endpoint list for any GLP or GH secretagogue study that measures blood pressure, body composition, or kidney function.
  2. Screen every participant for AVP deficiency and CKD before first exposure, and document RAAS inhibitor and diuretic co-medications.
  3. Stratify monitoring intensity by peptide half-life, long-acting agents require AVP-focused copeptin tracking; short-acting agents require more frequent natriuresis panels.
  4. Pre-specify electrolyte stopping rules and desmopressin caps in the protocol document before enrollment.
  5. Source compounds from suppliers providing verified purity data to eliminate formulation-driven fluid confounders.

Fluid-balance architecture is no longer optional in high-quality peptide research. Building it in from day one protects data integrity, participant safety, and the credibility of metabolic readouts across every endpoint.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/electrolytes-and-research-peptides-designing-fluid-balance-controls-for-glp-grow.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-09 14:05:212026-11-13 20:07:05Electrolytes and Research Peptides: Designing Fluid-Balance Controls for GLP, Growth-Hormone, and Metabolic Studies
Electrolytes, Diuretics, and Growth-Hormone Peptides: Interpreting Fluid Retention Without Misreading Body Composition

Electrolytes, Diuretics, and Growth-Hormone Peptides: Interpreting Fluid Retention Without Misreading Body Composition

November 5, 2026/0 Comments/in Uncategorized/by

A single dose of furosemide can drop the scale by two to four pounds overnight, none of it fat. Yet that number routinely gets recorded as "progress." Understanding electrolytes, diuretics, and growth-hormone peptides: interpreting fluid retention without misreading body composition is one of the most clinically important skills anyone tracking physique or health metrics needs to develop in 2026.

Sodium, potassium, hydration status, thiazide diuretics like hydrochlorothiazide (HCTZ), loop diuretics like furosemide, and growth-hormone-releasing peptides all move water in and out of tissues. When those shifts go unaccounted for, lean-mass and weight endpoints become meaningless noise.

Key Takeaways

  • Fluid retained or lost because of electrolytes, diuretics, or GH peptides is not fat gained or lost.
  • Bioelectrical impedance analysis (BIA) is highly sensitive to hydration status and electrolyte balance, often producing wildly inaccurate lean-mass readings.
  • Growth-hormone peptides cause dose-dependent, reversible water retention by altering sodium handling rather than increasing fat mass.
  • Diuretics deplete electrolytes alongside water, compounding measurement error and adding real cardiovascular risk.
  • Body composition should only be assessed after fluid status, medications, and measurement timing are standardized.

How Growth-Hormone Peptides Drive Fluid Retention

How Growth-Hormone Peptides Drive Fluid Retention

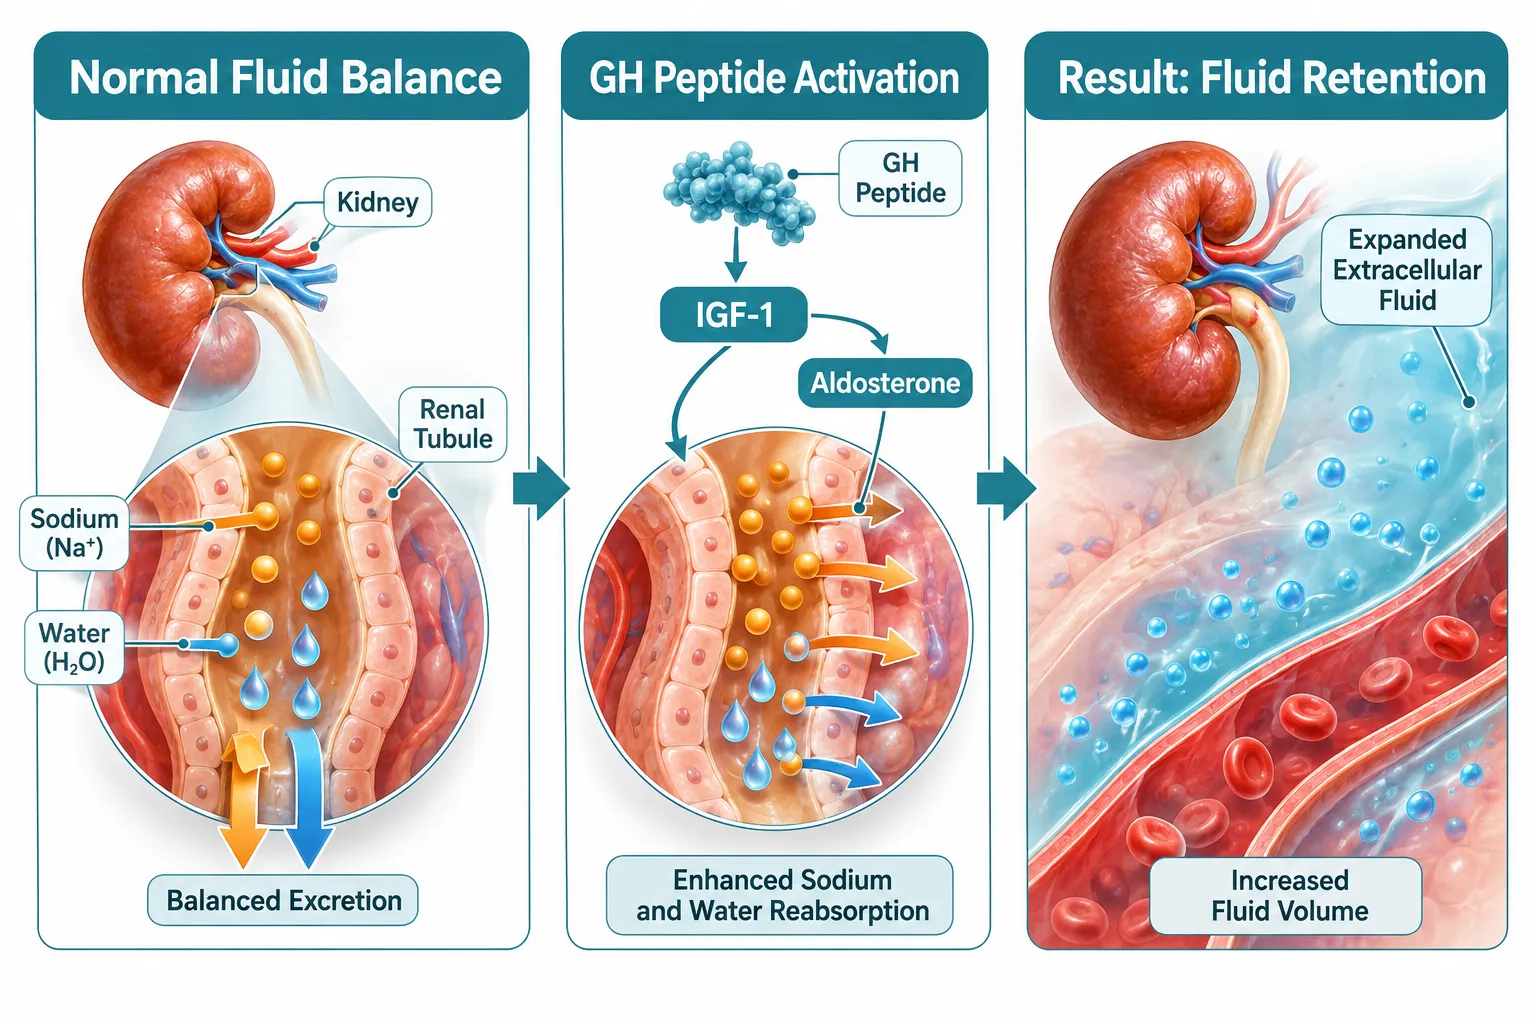
Growth-hormone secretagogues and GHRH analogs, the class of compounds that includes tesamorelin-based protocols, stimulate endogenous GH release. That GH pulse triggers an IGF-1 response that, in turn, promotes sodium and water reabsorption in the renal tubules. The result is an expansion of extracellular fluid volume that shows up almost immediately on the scale.

This mechanism is well-established. GH and GH-related peptides shift sodium-water handling rather than directly increasing adipose tissue. The water retention is dose-dependent: larger or more frequent administrations produce more pronounced fluid accumulation. Critically, the effect is reversible, fluid redistributes back toward baseline when dosing is reduced or discontinued.

"The scale going up during a GH peptide protocol almost always reflects water, not fat. Treating it as fat gain is a measurement error, not a physiology lesson."

For anyone following a tesa dosage for bodybuilding protocol, understanding this distinction prevents unnecessary caloric restriction that undermines the goal of the compound entirely.

Regulatory labeling updated in 2025-2026 now consistently highlights fluid retention as a primary monitoring parameter for GH-class products, reinforcing that practitioners must track it separately from true composition changes.


Why Diuretics Distort the Picture Further

Why Diuretics Distort the Picture Further

Diuretics operate through completely different mechanisms, yet they produce a mirror-image problem. HCTZ works on the distal tubule to block sodium-chloride co-transport, pulling water out through the kidneys. Furosemide, a loop diuretic, blocks a broader sodium-potassium-chloride transporter in the loop of Henle, producing faster and more dramatic fluid loss, along with significant potassium and magnesium depletion.

The clinical danger here is twofold:

  1. Measurement distortion: Rapid water loss makes the scale drop and BIA devices report falsely elevated lean-mass percentages, since the device interprets lower total body water as proportionally more muscle.
  2. Electrolyte depletion + exercise risk: Diuretic-driven hypokalemia combined with intense physical activity magnifies cardiac arrhythmia risk. This is not theoretical, it is a documented interaction that has ended athletic careers.

Combining diuretics with GH peptide protocols creates competing fluid signals. The peptide retains water; the diuretic flushes it. The body composition reading at any single point reflects whichever force is currently dominant, not actual tissue changes.

Compound Primary Fluid Action Electrolyte Effect BIA Impact
GH Peptides Increases extracellular water Mild sodium retention Falsely lower lean-mass %
HCTZ Reduces total body water Potassium/magnesium loss Falsely higher lean-mass %
Furosemide Rapid total body water loss Significant K+/Mg2+ depletion Severely distorted readings

Standardizing Assessment to Get Accurate Body Composition Data

Standardizing Assessment to Get Accurate Body Composition Data

The expert consensus in 2026 is clear: body composition should only be interpreted when fluid status, medications, and timing have been standardized. Without that foundation, even imaging-based methods like DEXA are affected, though less so than BIA.

BIA scales are the worst performers under variable hydration conditions. A person who drank an extra liter of water or took a diuretic the previous evening can see lean-mass readings shift by three to five pounds from one morning to the next with zero actual tissue change. For anyone researching peptide compounds and their effect on weight endpoints, this point cannot be overstated. Resources like what is the strongest peptide for weight loss often focus on fat oxidation mechanisms, but those mechanisms are invisible if the measurement tool is compromised by fluid noise.

A practical standardization protocol:

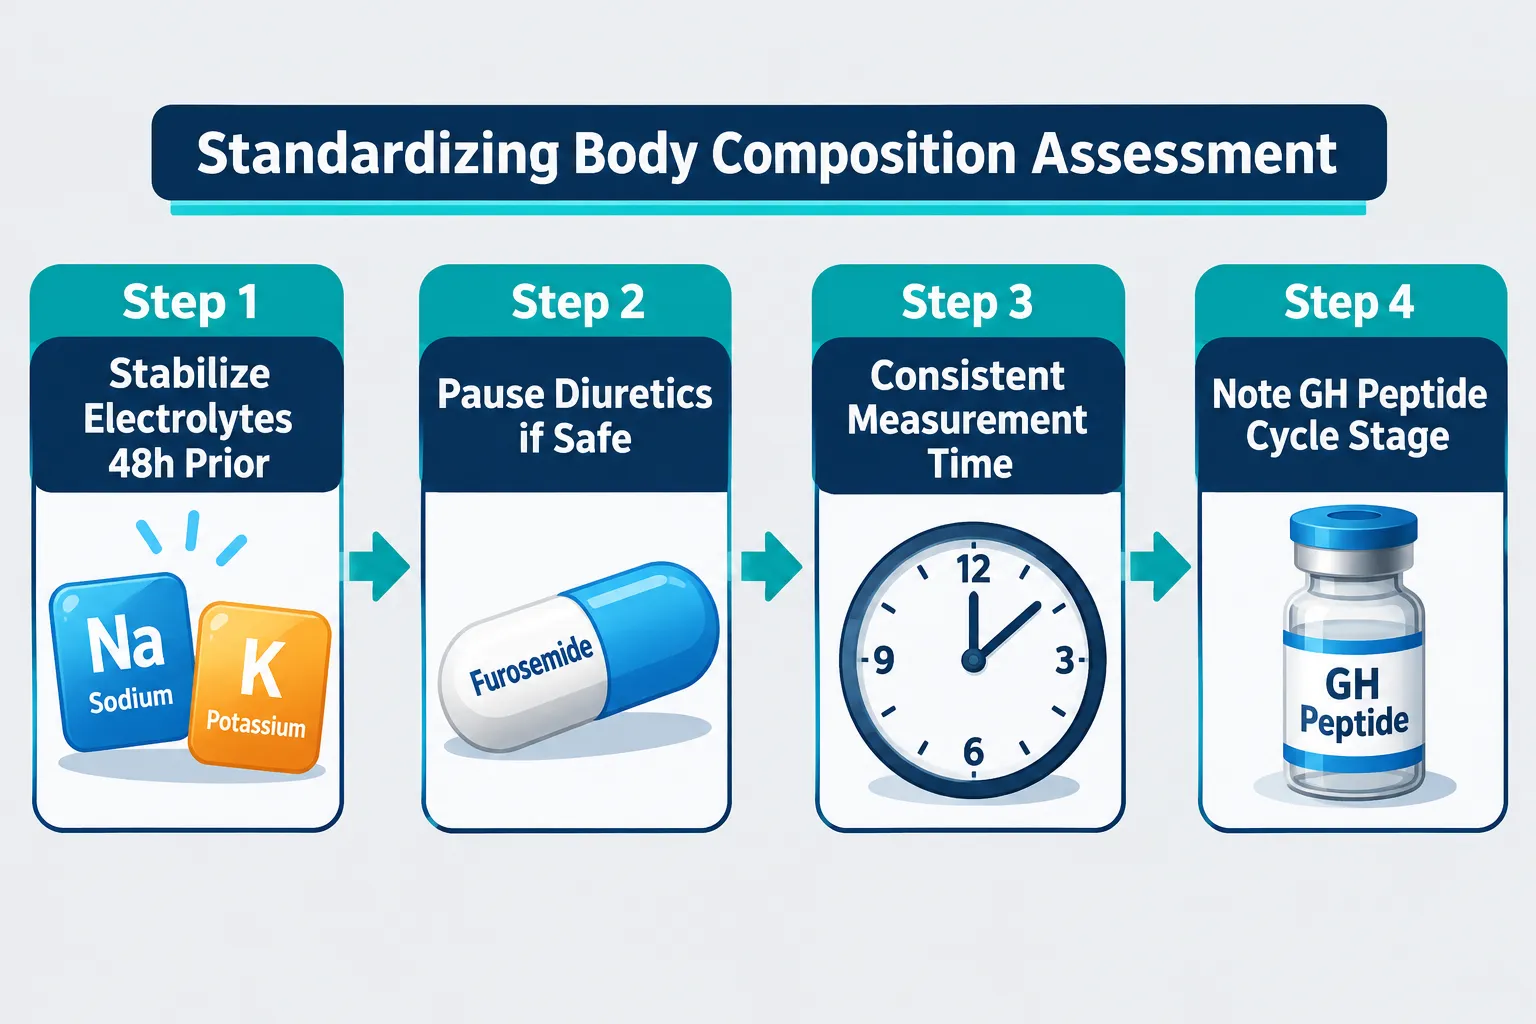
  • 48 hours before assessment: stabilize sodium and potassium intake; avoid high-sodium processed foods.
  • Morning of assessment: fasted state, consistent time (within 30 minutes of prior tests), post first void.
  • Medication pause: if clinically safe, pause diuretics for 48 hours before measurement; document GH peptide cycle stage.
  • Hydration: maintain consistent water intake; avoid heavy exercise the prior day.
  • Record confounders: note menstrual cycle phase, recent illness, travel, or unusual stress.

This protocol applies whether using BIA, DEXA, or hydrostatic weighing. The goal is to hold the fluid variable constant so that any change in the number genuinely reflects tissue change.

For those researching peptide mechanisms more broadly, the GLP-3 peptide signaling pathway article provides useful context on how peptide classes interact with metabolic endpoints differently, and how GLP-1 peptides affect body composition through appetite and metabolic routes rather than direct fluid retention pathways.

Looking ahead, body-composition tool manufacturers are expected to integrate hydration and medication flags directly into consumer and clinical devices, a development that would automatically alert users when a reading is likely compromised by fluid status.


Conclusion

Fluid retention from electrolyte shifts, diuretic use, or growth-hormone peptide protocols is one of the most common and least-corrected sources of body-composition measurement error. Recognizing that a rising scale during a GH peptide cycle reflects reversible water retention, not fat gain, and that furosemide or HCTZ "weight loss" reflects electrolyte depletion rather than fat reduction, is foundational to any honest tracking practice.

Actionable next steps:

  1. Standardize measurement conditions before drawing any conclusion from a body composition reading.
  2. Document current medications, including diuretics and peptide cycle stage, alongside every assessment.
  3. Use BIA readings only as directional trend data, not absolute values, whenever hydration or electrolyte status is in flux.
  4. If managing both diuretic and GH peptide protocols, consider imaging-based assessments at standardized intervals rather than relying on daily scale data.
  5. Consult a qualified clinician before pausing any prescribed diuretic for measurement purposes.

Accurate composition data is only possible when the fluid variable is controlled. Everything else is measuring water.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/electrolytes-diuretics-and-growth-hormone-peptides-interpreting-fluid-retention.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-05 14:03:452026-11-05 14:03:45Electrolytes, Diuretics, and Growth-Hormone Peptides: Interpreting Fluid Retention Without Misreading Body Composition
Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework

Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework

October 25, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Spironolactone and GLP or Growth-Hormone' in crisp white sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins, two balanced lines, no character near any edge. Background: clean editorial medical illustration showing kidney cross-section with aldosterone signaling arrows, potassium ion symbols, and molecular structure silhouettes in teal and gold on a dark navy field. Magazine-quality medical editorial aesthetic, high contrast, pharmaceutical research tone.","content":["Annotated mechanism-of-action diagram, landscape format (1536×1024), showing the mineralocorticoid receptor pathway in the distal convoluted tubule: four labeled stages left to right, 'Aldosterone Binds Receptor', 'Spironolactone Blocks Site', 'Sodium Excretion Rises', 'Potassium Retained', with thin callout arrows pointing to each stage, illustrated cross-section of renal tubule cells in center, teal-and-white palette on a light gray background, clean medical editorial style, no pricing or checkmarks.","Three-panel labeled comparison guide, landscape format (1536×1024), comparing potassium monitoring timelines: Panel 1 labeled 'Week 1 Check' showing a blood draw vial icon with '5.0 mmol/L threshold' callout; Panel 2 labeled 'Monthly x3 Months' with a calendar icon and 'Creatinine + K+' callout; Panel 3 labeled 'Quarterly Then 6-Monthly' with a line graph icon and 'Renin Target' callout. Navy, teal, and amber palette on white background, clinical infographic style, bold panel headings, short bullet labels only.","Split-screen editorial illustration, landscape format (1536×1024): left half shows a GLP-1 receptor agonist pathway diagram with labeled nodes, 'Incretin Effect', 'Plasma Volume Drop', 'NT-proBNP Reduction', 'Weight Loss', connected by flow arrows in green and slate; right half shows a spironolactone aldosterone-blockade pathway with labeled nodes, 'MRA Blockade', 'Fluid Offloading', 'BP Normalization', 'K+ Rise Risk', in teal and navy. Center dividing line with label 'Integrated Cardiometabolic Framework'. Clean white background, bold callout lines, medical editorial polish.","Numbered step-by-step process flow diagram, landscape format (1536×1024), showing five horizontal stages of a combined spironolactone plus GLP-peptide monitoring protocol: Step 1 'Baseline Labs: K+, eGFR, Renin, Aldo'; Step 2 'Start or Titrate Spiro'; Step 3 'Day 3-5: Adjust K+ Supplements'; Step 4 'Week 1: Recheck K+ and Creatinine'; Step 5 'Month 2-3: Reassess Renin, NT-proBNP'. Each step in a rounded card, connected by bold directional arrows, teal-to-navy gradient across cards, amber warning badge on Step 4, clean sans-serif labels, white background, clinical protocol aesthetic."]

Professional landscape hero image () with a reading "Spironolactone and GLP or Growth-Hormone". CRITICAL TYPOGRAPHY RULES:

Fewer drugs in clinical medicine carry as many overlapping metabolic consequences as spironolactone, a potassium-sparing diuretic that simultaneously lowers blood pressure, reshapes fluid distribution, and alters how every co-administered agent affects renal electrolyte handling. As research into GLP-1 receptor agonists and growth-hormone peptides expands into cardiometabolic territory, the intersection with mineralocorticoid receptor antagonism (MRA) has become impossible to ignore. Understanding the Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework is increasingly essential for clinicians and researchers navigating this overlapping landscape.

Key Takeaways

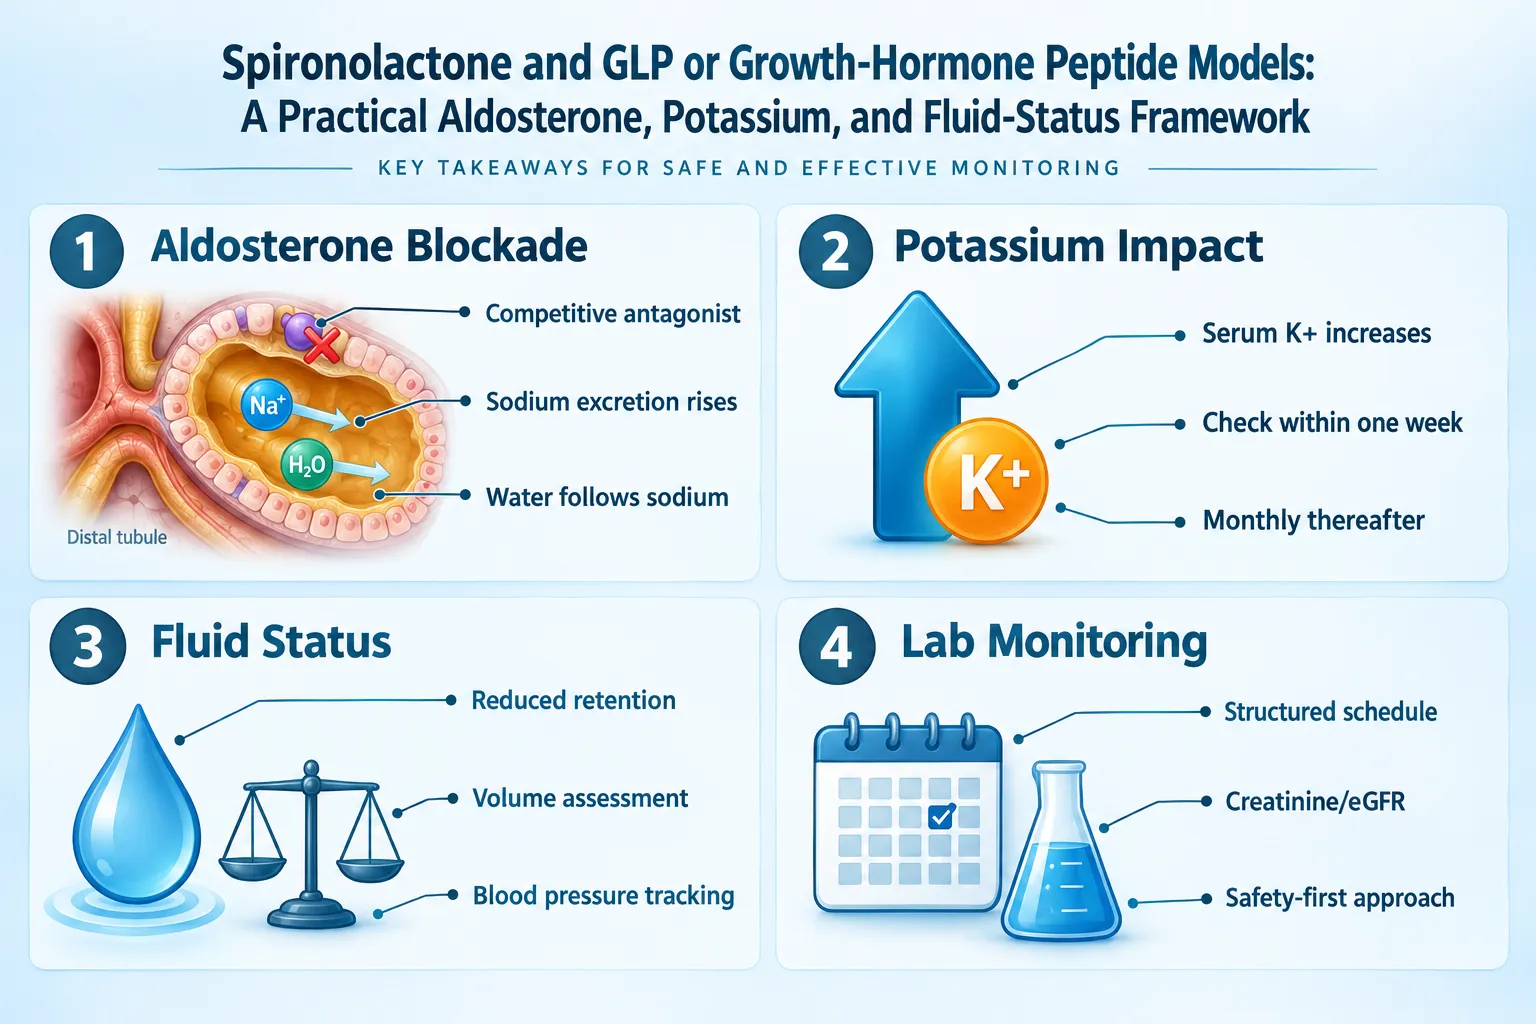
  • Spironolactone competitively blocks aldosterone at the distal tubule, raising serum potassium and reducing sodium and water retention, effects that require structured laboratory monitoring.
  • Potassium must be checked within one week of starting or up-titrating spironolactone, then monthly for three months, quarterly for a year, and every six months thereafter.
  • GLP-1 and dual incretin agonists produce early plasma volume reductions and NT-proBNP decreases that can compound or mask fluid changes from mineralocorticoid blockade.
  • No formal co-therapy guideline currently covers combined spironolactone and GLP or growth-hormone peptide use; any integrated framework is built by extrapolating from MRA, primary aldosteronism, and heart failure evidence.
  • Renin is the primary biochemical titration target for spironolactone in aldosterone-excess states; potassium serves as both a safety marker and a key interpretive variable.

How Spironolactone Changes Aldosterone, Potassium, and Fluid Status

How Spironolactone Changes Aldosterone, Potassium, and Fluid Status

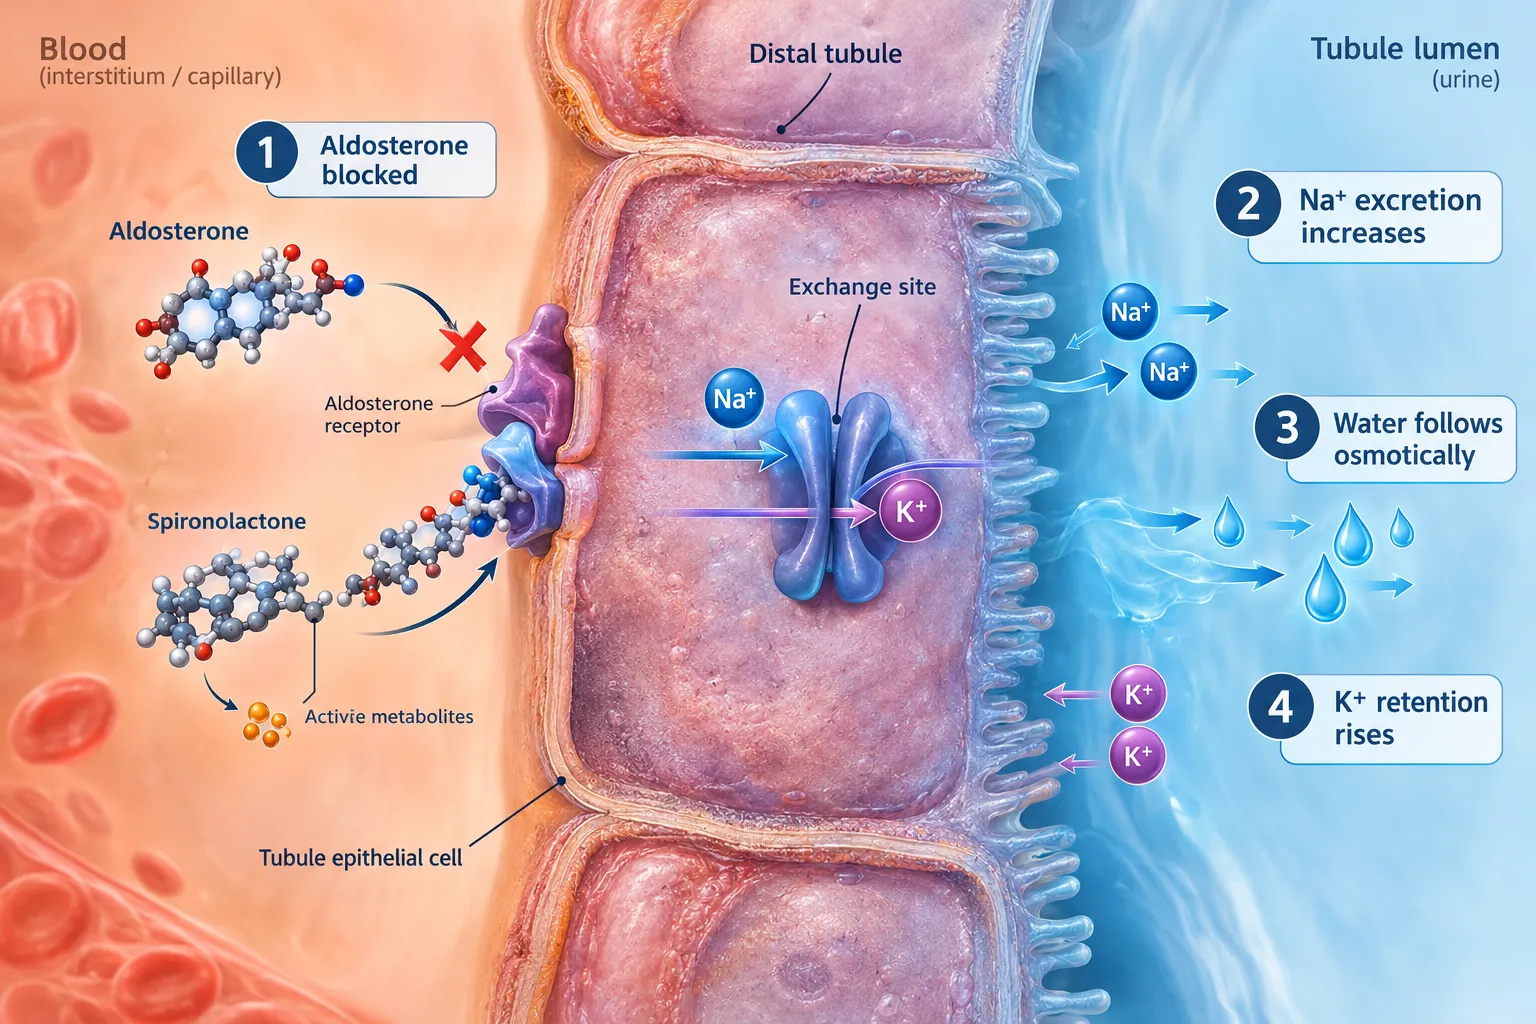
Spironolactone's pharmacology is specific and mechanistically clean. It and its active metabolites act as competitive antagonists at the aldosterone-dependent sodium-potassium exchange site in the distal convoluted tubule. When aldosterone is blocked, sodium excretion rises, water follows, and, critically, potassium is retained rather than excreted.

This mechanism explains why the drug is first-line medical therapy for primary aldosteronism, resistant hypertension, and heart failure with reduced ejection fraction. In aldosterone-excess states, starting spironolactone at 12.5-25 mg daily with careful titration typically normalizes serum potassium within three to five days. That rapid shift means potassium supplements already being taken by the patient often need reduction or discontinuation by days two to four to prevent rebound hyperkalemia.

Why Potassium Is Both a Safety Marker and a Diagnostic Variable

Potassium's role in a spironolactone framework goes beyond safety. Low serum potassium can artificially lower measured aldosterone, potentially misleading diagnosis or obscuring the true degree of aldosterone excess. As a result, potassium must be corrected and then tracked alongside renin and aldosterone throughout therapy, not just checked once at baseline.

The treatment target in primary aldosteronism is an unsuppressed renin, which signals adequate mineralocorticoid receptor blockade. This renin-centered titration strategy is a cornerstone of the broader Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework when applied to aldosterone-driven conditions.

"Renin normalization is the biochemical proof of adequate mineralocorticoid blockade, potassium is the safety guardrail."


The Monitoring Schedule That Anchors Any Practical Framework

The Monitoring Schedule That Anchors Any Practical Framework

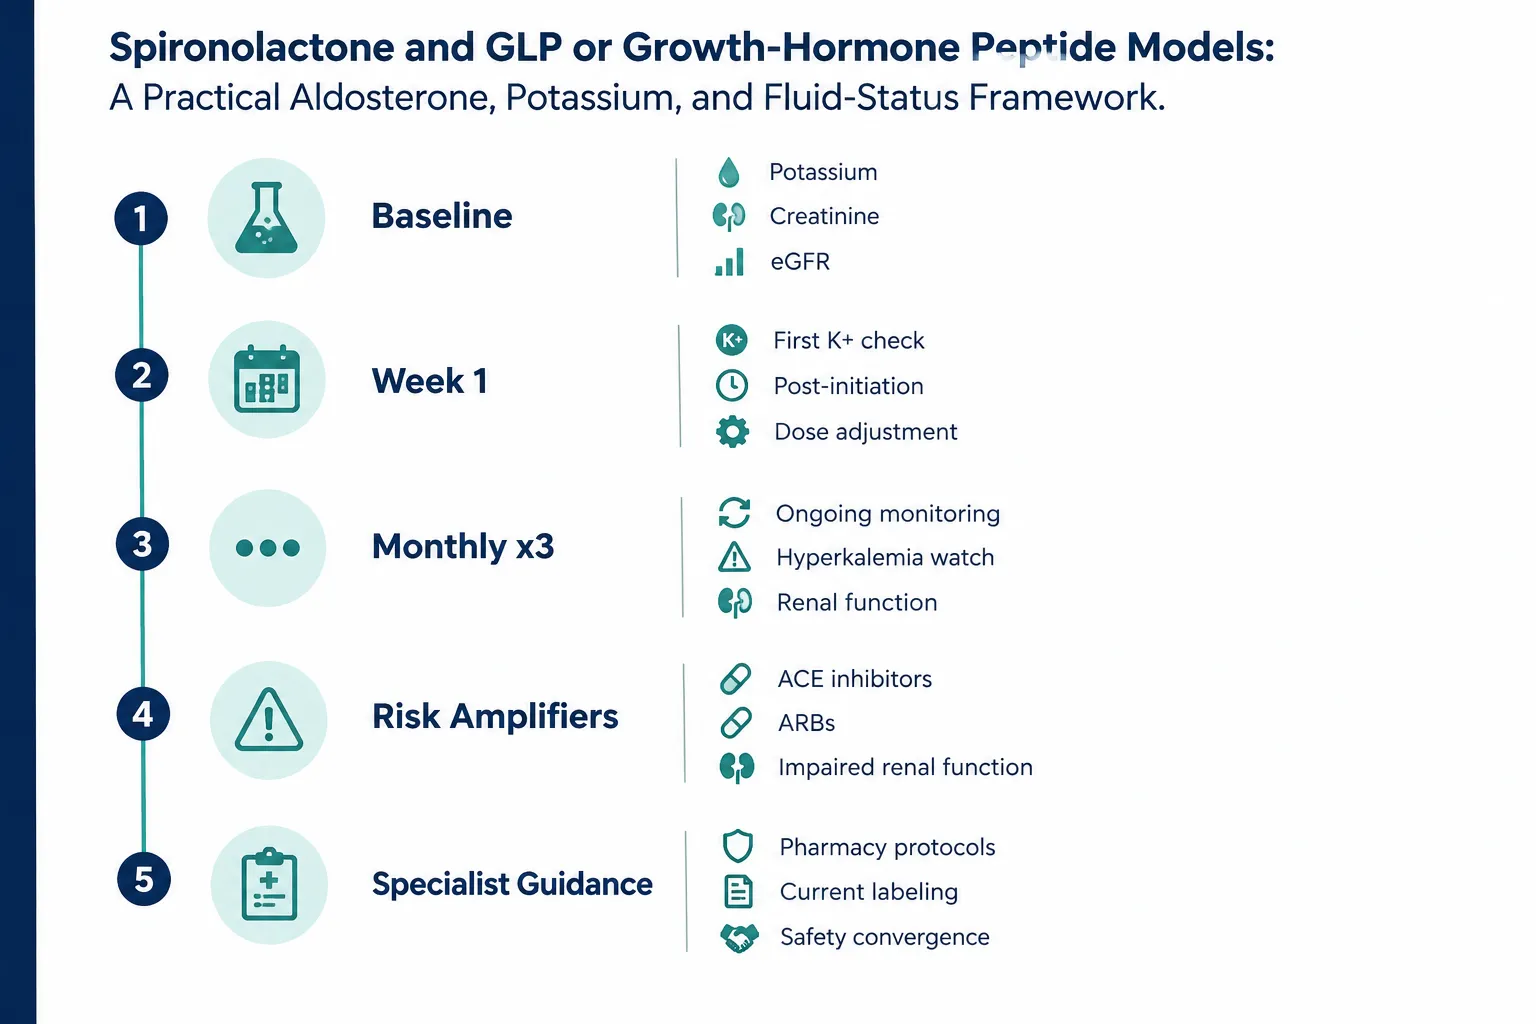
Hyperkalemia is the central safety concern with spironolactone. Risk amplifies with impaired renal function, concurrent ACE inhibitors, ARBs, and any agent that independently raises potassium. Current labeling and specialist pharmacy guidance converge on a structured monitoring schedule:

Timepoint Parameters to Check
Baseline Potassium, creatinine/eGFR, blood pressure, renin, aldosterone
1 week after starting or dose change Potassium, creatinine
Monthly for first 3 months Potassium, creatinine
Every 3 months, months 3-12 Potassium, creatinine
Every 6 months thereafter Potassium, creatinine
2-3 months after initiation Renin (to assess titration adequacy)

Action thresholds are equally important:

  • Potassium above 5.0 mmol/L at baseline: spironolactone is contraindicated.
  • Potassium 5.5-6.0 mmol/L during therapy: reduce dose or hold temporarily.
  • Potassium above 6.5 mEq/L: emergency intervention required.
  • Creatinine above approximately 4 mg/dL: consider discontinuation.

This schedule forms the operational backbone of any aldosterone, potassium, and fluid-status model regardless of what co-therapies are layered on top.


Where GLP and Growth-Hormone Peptide Models Intersect

Where GLP and Growth-Hormone Peptide Models Intersect

The connection between incretin-based therapies and spironolactone is not arbitrary. A 2026 network meta-analysis on obstructive sleep apnea found both spironolactone and the dual GLP-1/GIP agonist tirzepatide among the most effective interventions for reducing apnea-hypopnea index, a finding that highlights converging cardiometabolic benefits across MRA and incretin pathways.

GLP-1 receptor agonists also produce measurable early reductions in plasma volume and NT-proBNP before significant weight loss occurs, suggesting cardiac-specific and potentially volume-modulating effects. When these agents run concurrently with spironolactone, several interactions become clinically relevant:

  • Volume depletion risk: Both drug classes reduce fluid retention through distinct pathways. Combined use may produce greater blood pressure reduction and orthostatic symptoms than either agent alone.
  • NT-proBNP interpretation: GLP-1-driven NT-proBNP reductions can obscure the fluid-status signal that clinicians use to assess heart failure trajectory on MRA therapy.
  • Weight and blood pressure reassessment: Significant weight loss from GLP or growth-hormone peptide protocols reduces aldosterone secretion independently, which can shift the spironolactone dose requirement downward over time.

Research into GLP-3 peptide signaling pathways and related GLP-3 peptide products is increasingly part of this evolving framework, as investigators examine how incretin-family peptides modulate fluid and metabolic endpoints beyond classical glucoregulation. Similarly, mitochondrial-targeted agents such as the SS-31 peptide and research around SS-31 peptide benefits suggest additional cardiorenal pathways that may eventually intersect with MRA therapy in translational models.

It is important to state clearly: as of 2026, no dedicated guideline or randomized trial directly addresses a formalized protocol for combined spironolactone and GLP-1 or growth-hormone peptide co-therapy. Any integrated model must extrapolate from well-established MRA monitoring schedules, incretin-related volume data, and cardiometabolic risk frameworks.


Building a Practical Combined Protocol

A synthesized, non-official practical protocol for the Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework would include:

  1. Baseline panel: Blood pressure, volume status assessment, potassium, creatinine/eGFR, renin, aldosterone, NT-proBNP, and body weight before initiating or up-titrating spironolactone.
  2. Early potassium management: Expect potassium normalization within three to five days; reduce or stop potassium supplements by days two to four with close monitoring.
  3. Week-one check: Recheck potassium and creatinine; adjust dose if thresholds are approached.
  4. Monthly monitoring: Continue for the first three months; include symptom-based fluid assessment, weight trends, edema, orthostatic symptoms.
  5. Renin reassessment at two to three months: Titrate spironolactone toward an unsuppressed renin while tracking potassium and creatinine.
  6. GLP/peptide-specific additions: Track NT-proBNP and weight trajectory; reassess spironolactone dose if significant weight loss alters aldosterone secretion; watch for additive volume depletion.

Researchers following this area may also find value in reviewing lab-tested peptides standards and emerging data on combination agents like cagrilinitide peptide, which represents dual-mechanism incretin modulation relevant to the cardiometabolic overlap with MRA therapy.


Conclusion

The Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework is not yet a formal guideline construct, but the clinical need for one is real and growing. Spironolactone's well-characterized effects on aldosterone, potassium, and fluid balance provide a rigorous structural foundation. Layering GLP-1 or growth-hormone peptide effects on top requires extending that foundation to include volume-depletion vigilance, NT-proBNP trending, and weight-driven reassessment of MRA dosing.

Actionable next steps for clinicians and researchers:

  • Apply the structured potassium and creatinine monitoring schedule from established MRA labeling as a non-negotiable baseline.
  • Add NT-proBNP and weight trending when any incretin-class or growth-hormone peptide is co-administered.
  • Reassess renin at two to three months and recalibrate spironolactone dose if body weight changes significantly.
  • Treat potassium simultaneously as a safety guardrail and a diagnostic variable when interpreting aldosterone status.
  • Continue monitoring the emerging literature, this intersection will likely produce dedicated guidance as GLP-based co-therapy becomes more common across cardiometabolic practice.
https://www.puretestedpeptides.com/wp-content/uploads/2026/10/spironolactone-and-glp-or-growth-hormone-peptide-models-a-practical-aldosterone.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-25 13:03:542026-11-13 20:06:52Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework
CJC-1295, Ipamorelin, and Tesamorelin: How to Compare GH Secretagogues by Exposure and Endpoint Timing

CJC-1295, Ipamorelin, and Tesamorelin: How to Compare GH Secretagogues by Exposure and Endpoint Timing

October 20, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'CJC-1295, Ipamorelin, and Tesamorelin' in crisp white sans-serif on a deep navy semi-transparent panel, centered with 8% safe margins from every edge. Background: high-resolution editorial illustration of three overlapping pharmacokinetic curve lines in teal, amber, and electric blue on a dark scientific grid background, suggesting GH pulse timing and exposure windows. Clean, clinical, magazine-quality aesthetic with subtle molecular structure motifs in the deep background. Modern, authoritative, science-forward composition.","content":["Four-panel labelled comparison infographic (1536×1024) on a clean white background with teal-and-navy palette. Panel 1: 'CJC-1295 with DAC', shows a wide flat pharmacokinetic curve labeled 'Days-long exposure', '~8-day half-life', 'Blunted pulsatility'. Panel 2: 'CJC-1295 no DAC', shows a sharp narrow peak labeled 'Minutes-scale PK', 'Pulse-matched dosing', 'GHRH receptor reset'. Panel 3: 'Ipamorelin', shows a rapid spike curve labeled '2-hour half-life', 'Ghrelin-receptor pathway', 'Sub-day endpoints'. Panel 4: 'Tesamorelin', shows a short PK curve beside a long clinical outcome arrow labeled 'Minutes PK / Months outcomes', 'VAT reduction endpoint'. Callout lines, editorial medical-guide polish, thin panel dividers.", "Annotated mechanism-of-action diagram (1536×1024) on a cool grey scientific background. Center: a stylized pituitary gland with two labeled receptor pathways branching outward, left branch labeled 'GHRH Receptor' with callout arrows pointing to 'CJC-1295 (DAC and no-DAC)' and 'Tesamorelin'; right branch labeled 'Ghrelin / GHS Receptor' with callout arrow to 'Ipamorelin'. Below each branch: short labeled boxes showing 'GH Pulse Amplitude', 'IGF-1 Rise (weeks)', 'Receptor Recovery Window'. Color-coded lines in teal, amber, and violet. Clean anatomical illustration style, precise callout lines, clinical editorial quality, no full sentences as image text.", "Split-screen editorial comparison image (1536×1024). Left panel: deep blue background showing a stylized timeline card with three rows labeled 'Days 1-7 Endpoint: IGF-1 rise', 'Weeks 4-8 Endpoint: Body composition', 'Months 3-6 Endpoint: VAT reduction', each row has a small colored dot matching the peptide color code. Right panel: warm teal background showing a sampling-density diagram, a horizontal axis labeled 'Measurement Frequency' with markers for 'Single fasted AM draw', 'Weekly IGF-1', 'Monthly DEXA', 'Quarterly MRI-VAT'. Thin connecting callout lines. Clean, data-visualization style, high contrast, editorial polish, fully labeled panels inside 5% safe margin."]

Professional landscape hero image () with a reading "CJC-1295, Ipamorelin, and Tesamorelin". CRITICAL TYPOGRAPHY RULES:

Most discussions of growth hormone secretagogues revolve around dosing protocols or stack combinations. Far fewer address the more fundamental question: does the duration of drug exposure actually match the biological endpoint being measured? For CJC-1295, Ipamorelin, and Tesamorelin, answering that question changes how these compounds should be selected, dosed, and evaluated in practice.

Key Takeaways

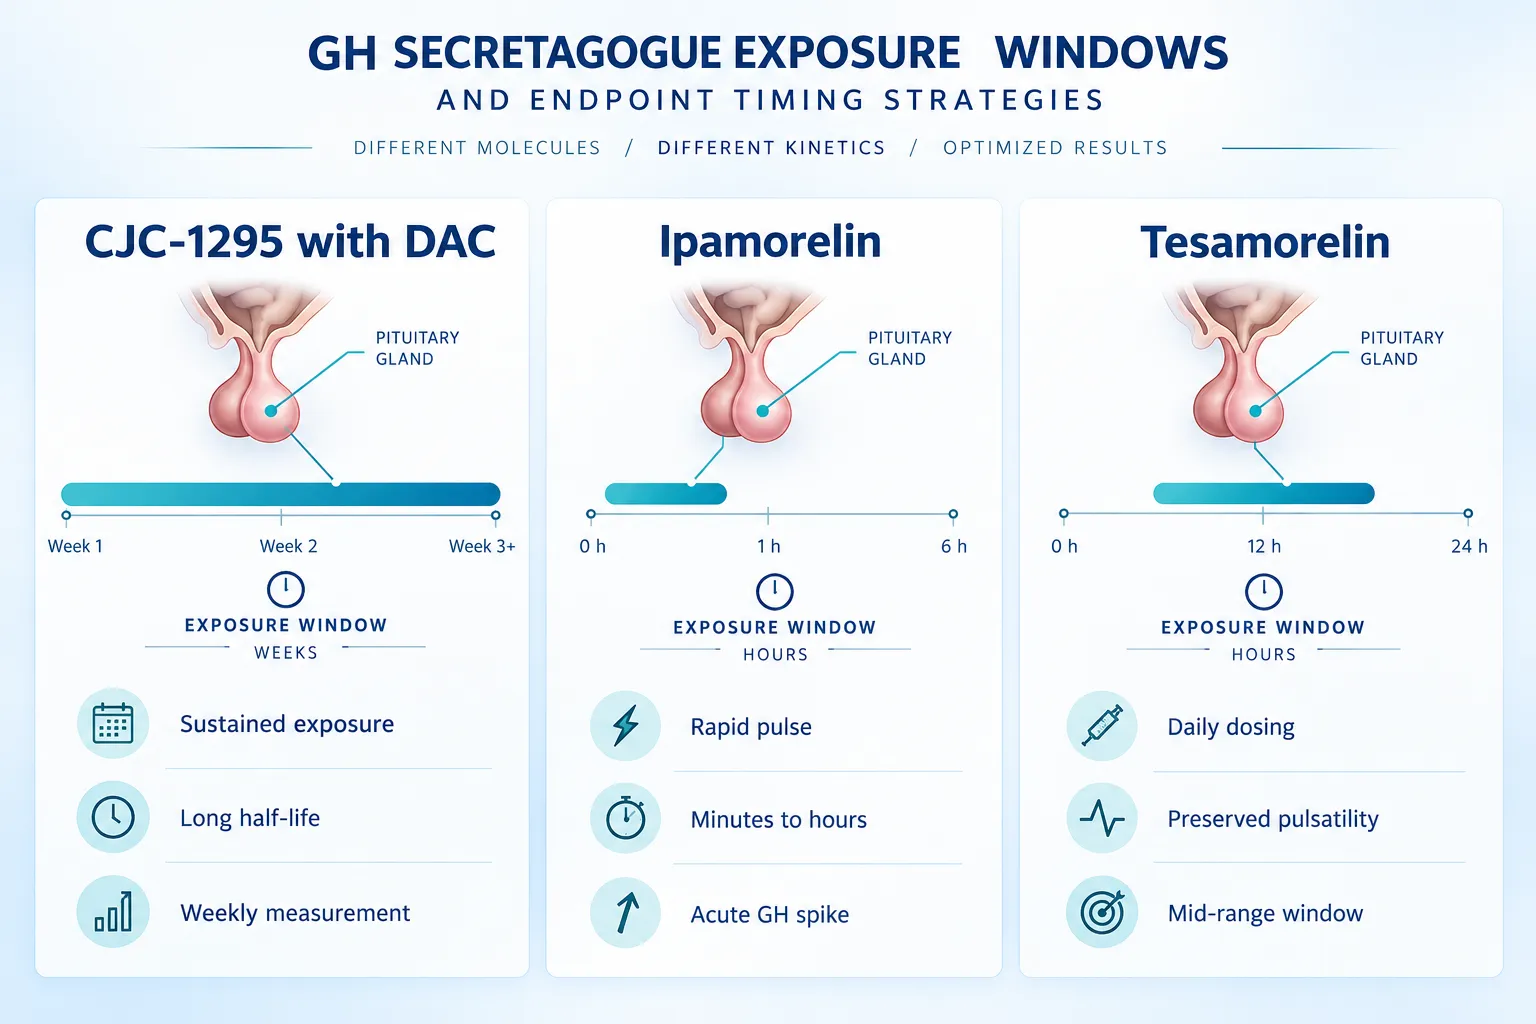
  • CJC-1295 with DAC, CJC-1295 without DAC, Ipamorelin, and Tesamorelin have exposure windows that span minutes to weeks, requiring different endpoint measurement strategies.
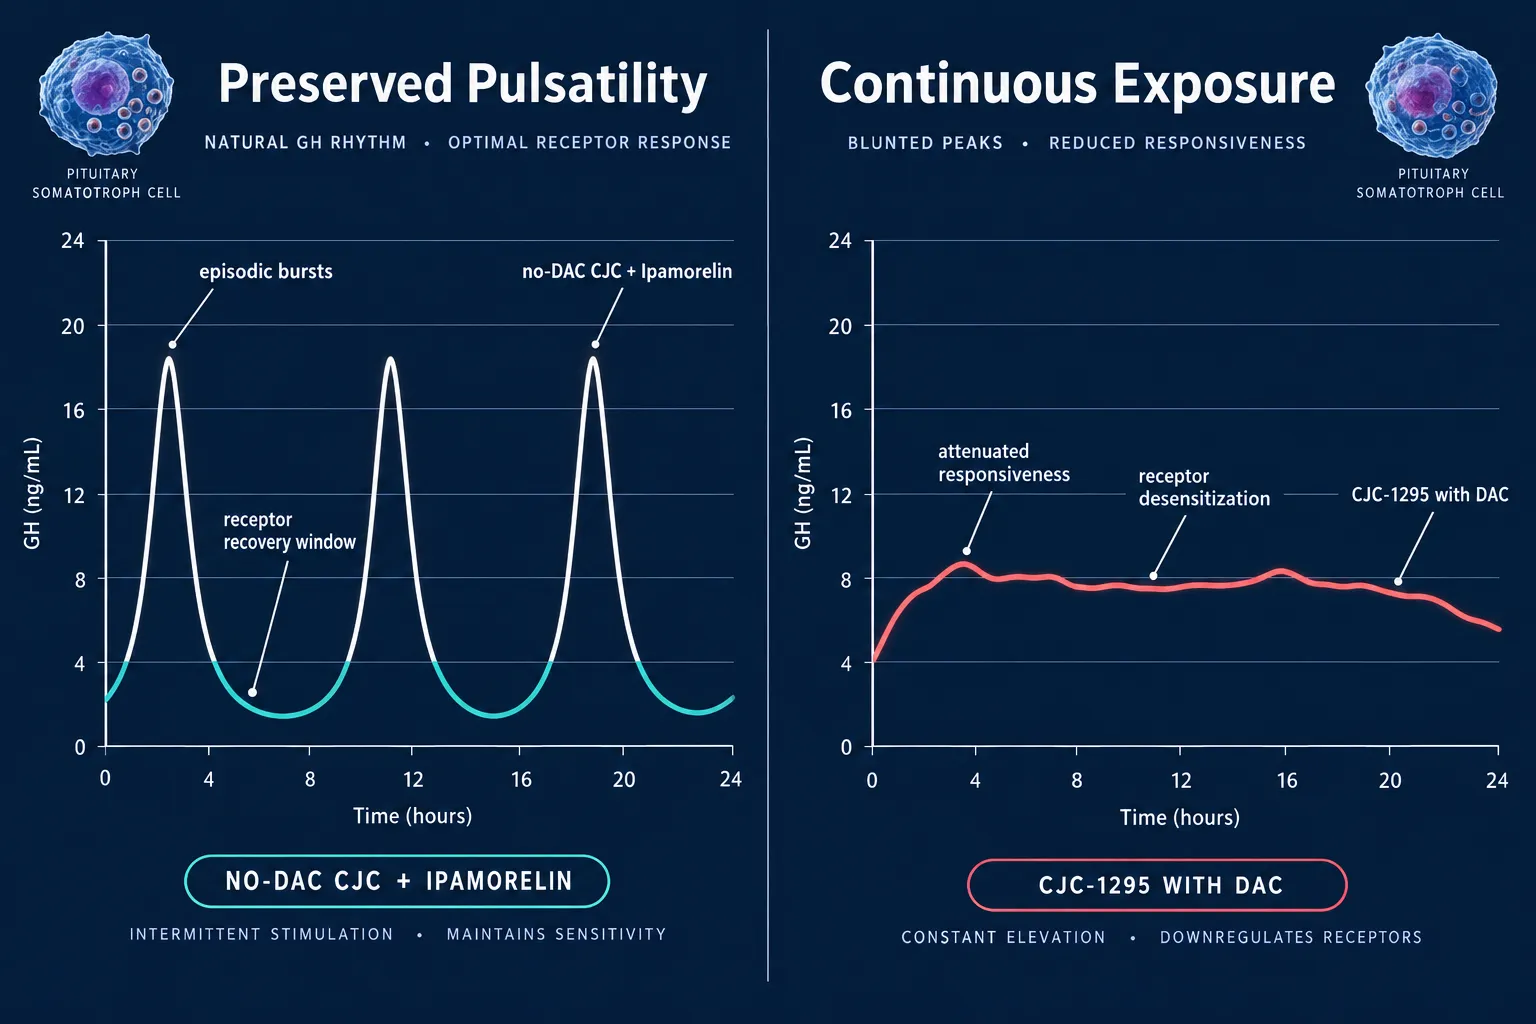
  • Pulsatility is a core design principle: compounds that preserve natural GH pulse architecture may produce better downstream receptor sensitivity than those that sustain continuous exposure.
  • Tesamorelin has the most robust clinical dataset of any GH secretagogue, with visceral adipose tissue (VAT) reduction as its validated primary endpoint.
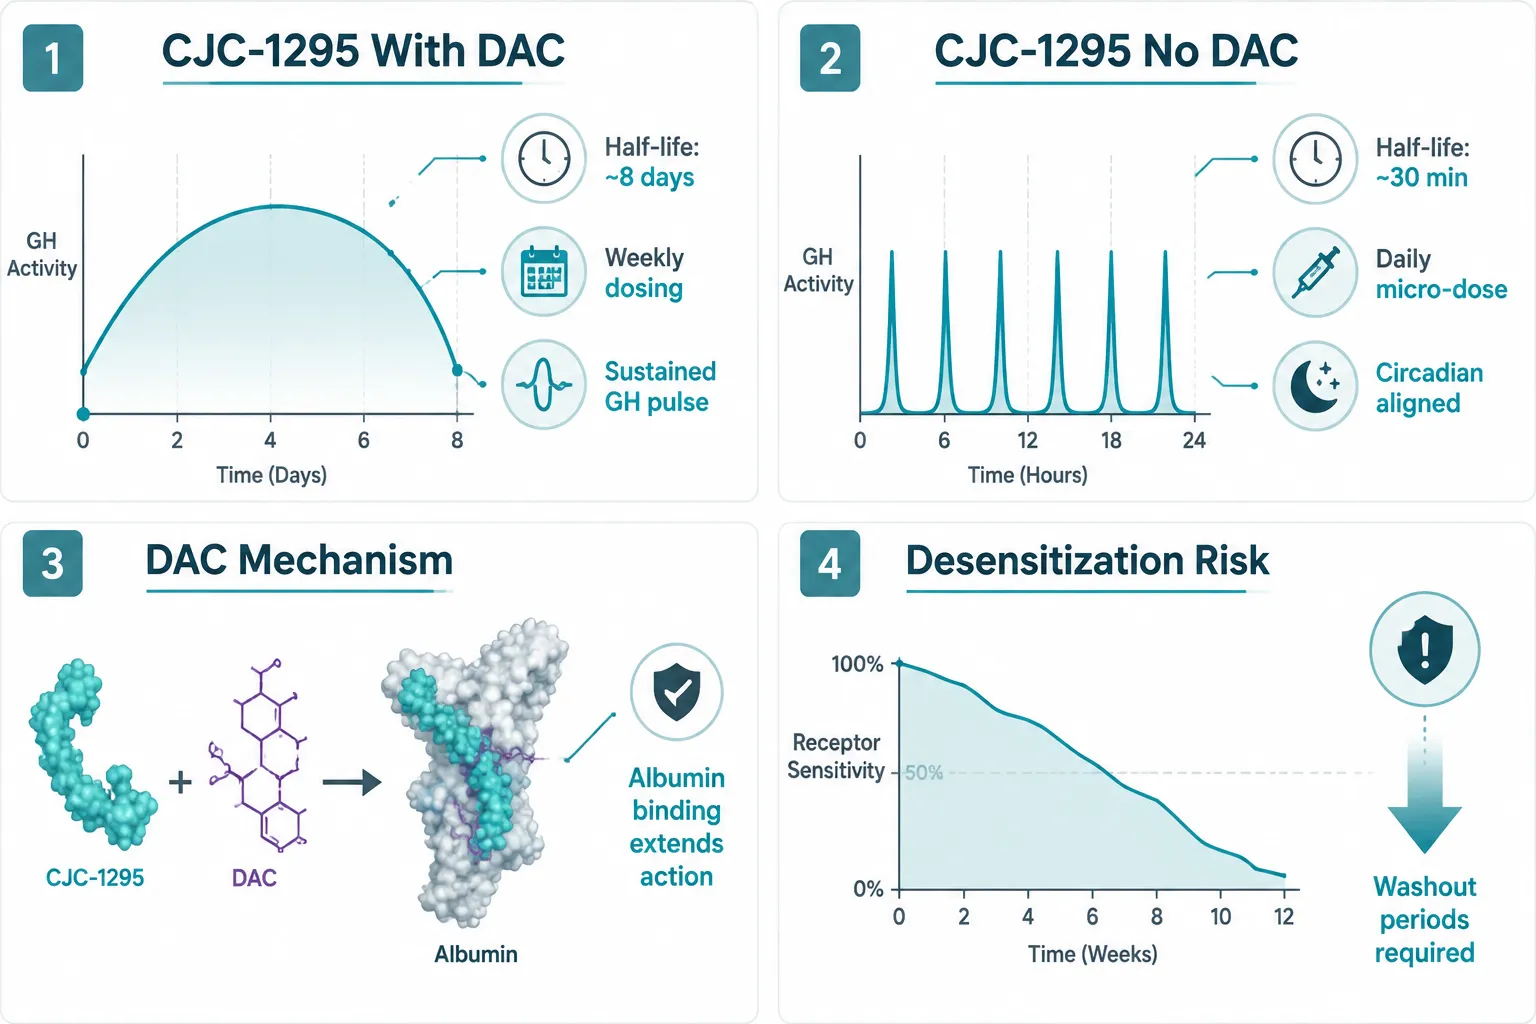
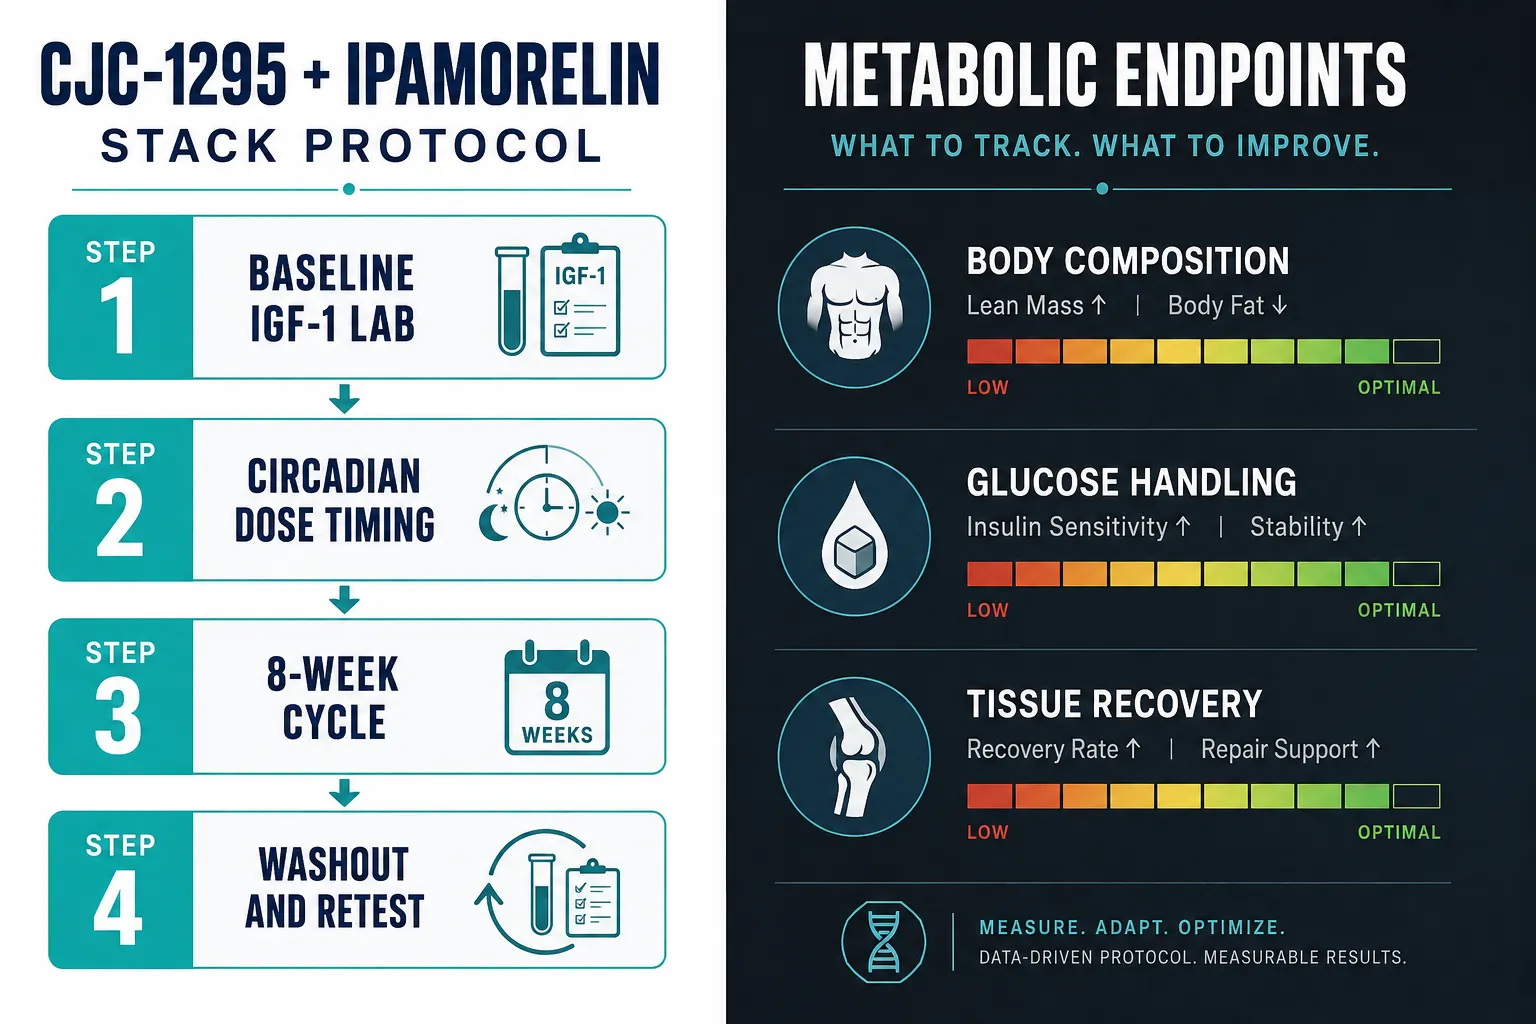
  • IGF-1 is a useful surrogate for CJC-1295 and Ipamorelin stacks, but requires 4-8 weeks of dosing before meaningful elevation appears.
  • Matching sampling density to the compound's exposure window is as important as the protocol itself.

Understanding Exposure Windows Across GH Secretagogues

Understanding Exposure Windows Across GH Secretagogues

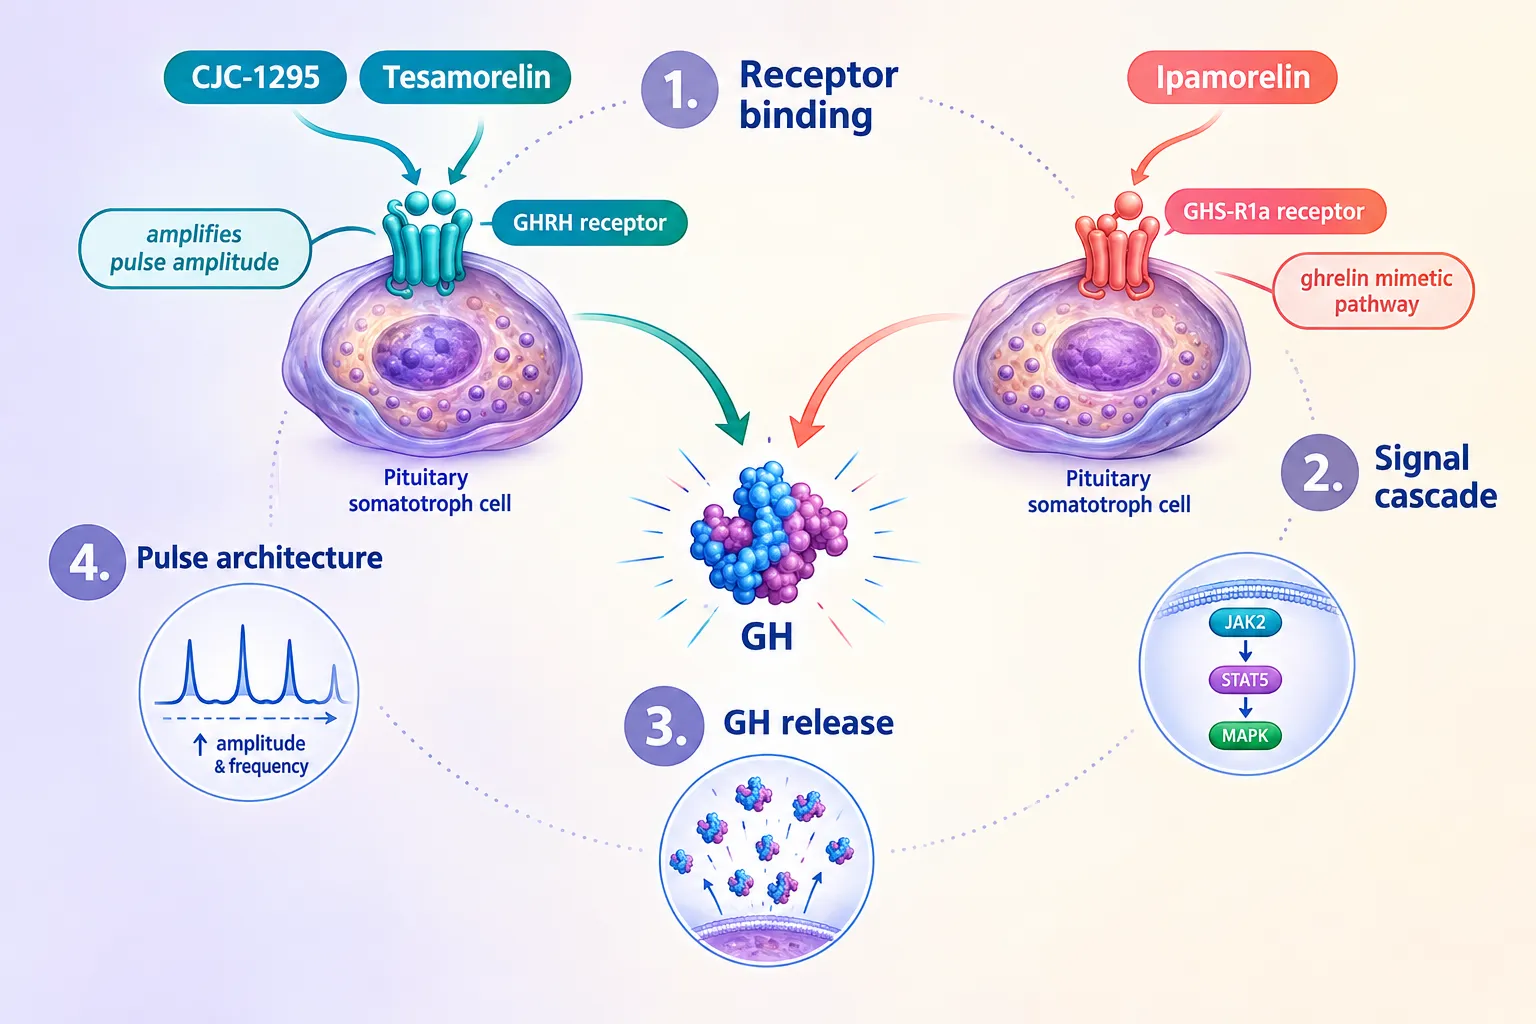
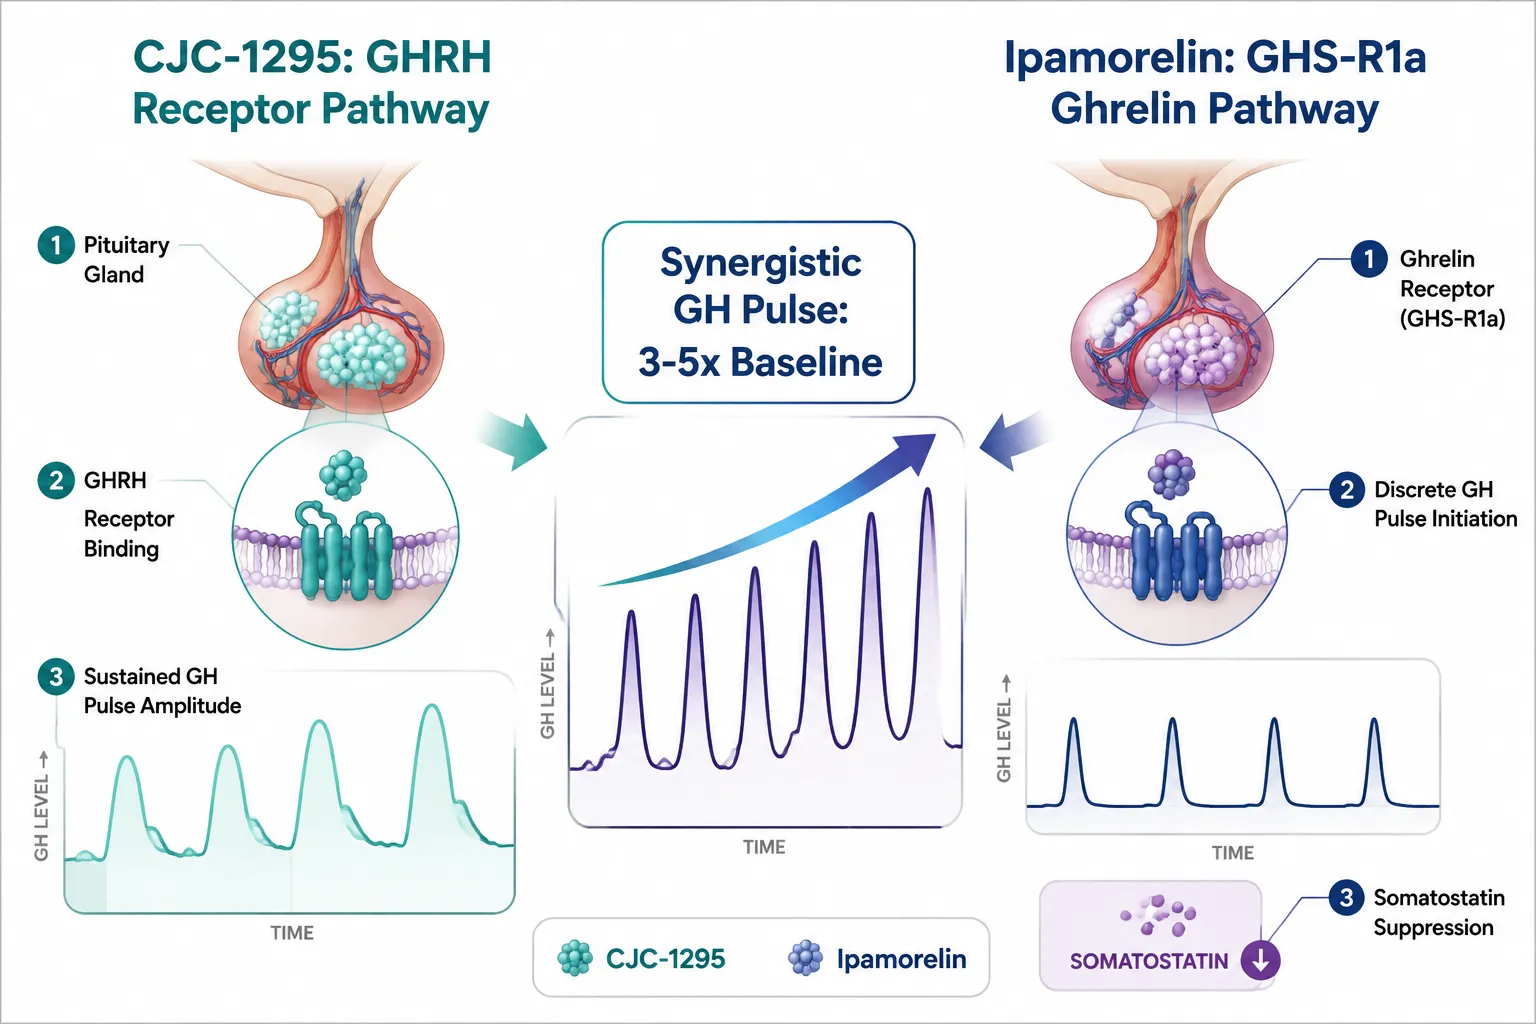
The phrase "GH secretagogue" covers two mechanistically distinct classes. GHRH analogues, CJC-1295 (both formulations) and Tesamorelin, bind the pituitary GHRH receptor and amplify GH pulse amplitude. Ghrelin mimetics like Ipamorelin act on the GHS-R1a receptor, triggering GH release through a separate pathway. When stacked, the two classes work synergistically, driving pulse amplitude higher than either can achieve alone.

What separates these agents most practically is not mechanism but exposure duration:

Compound Approximate Half-Life Exposure Window
CJC-1295 with DAC ~8 days Days to weeks
CJC-1295 without DAC (Mod GRF 1-29) ~30 minutes Hours
Ipamorelin ~2 hours Sub-day
Tesamorelin ~26 minutes Hours (PK); months (clinical)

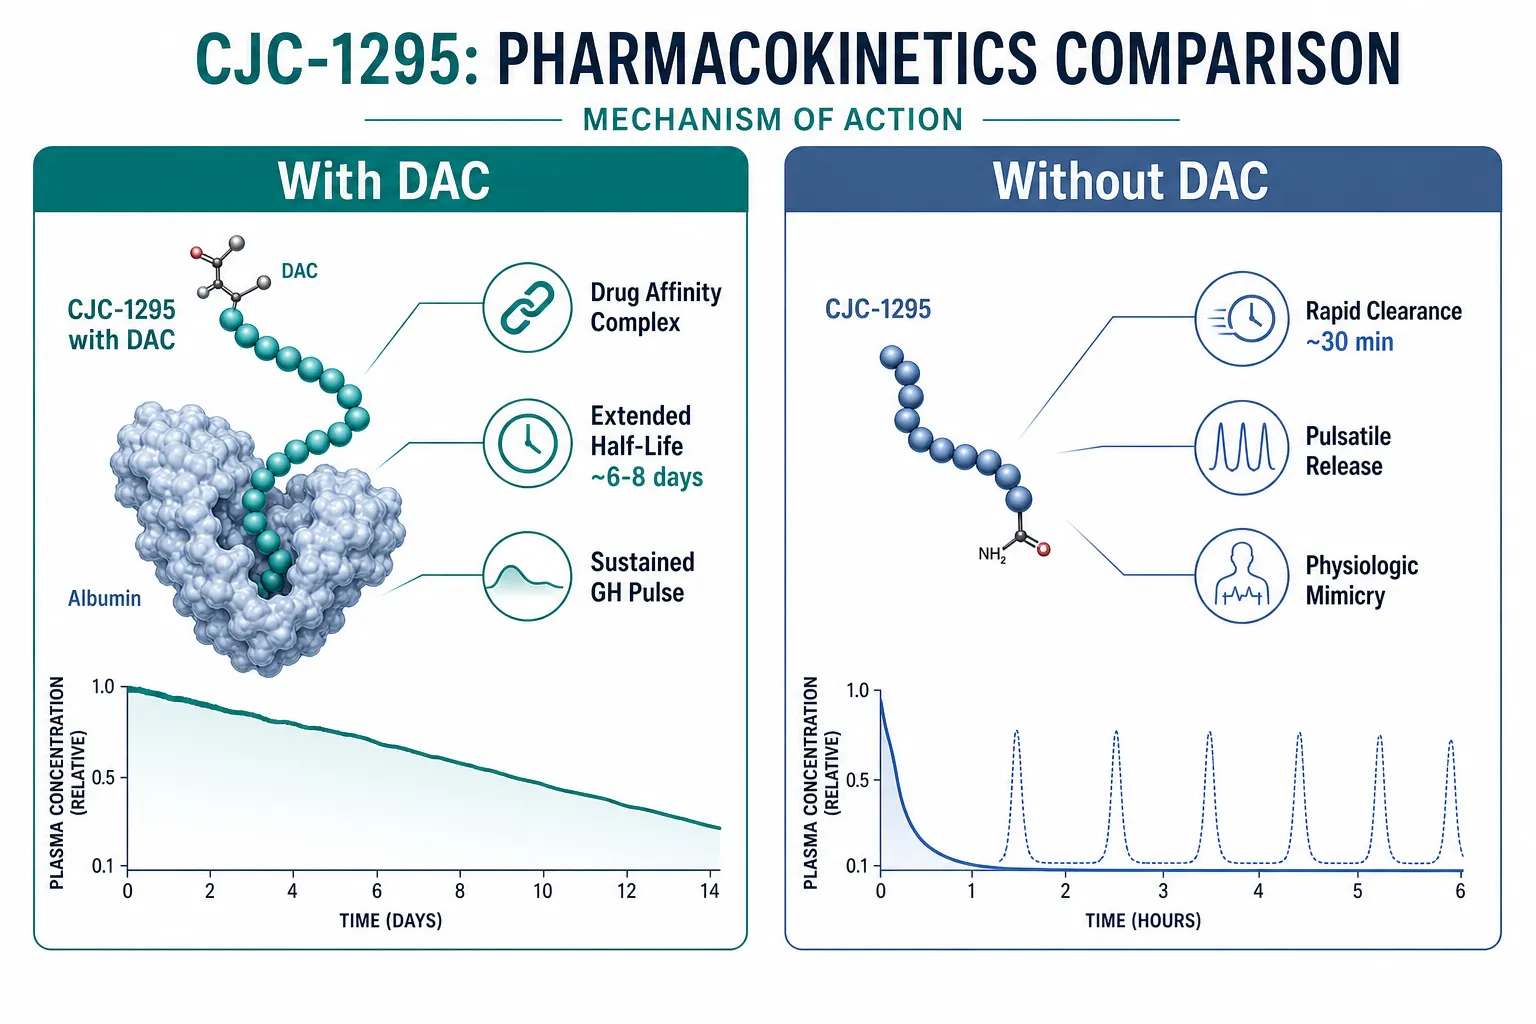
CJC-1295 with DAC uses a Drug Affinity Complex (DAC) technology that binds albumin, extending circulating half-life dramatically. The trade-off is a blunting of pulsatile GH release, replacing episodic peaks with a sustained tonic elevation. CJC-1295 without DAC (often called Mod GRF 1-29) behaves more like endogenous GHRH: it raises one pulse and clears within the hour, allowing the pituitary to recover before the next stimulation.

Understanding CJC-1295 and Ipamorelin dosing principles becomes meaningfully clearer once exposure windows are mapped to intended endpoints.


How CJC-1295, Ipamorelin, and Tesamorelin Differ in Pulse Architecture and Receptor Recovery

How CJC-1295, Ipamorelin, and Tesamorelin Differ in Pulse Architecture and Receptor Recovery

Pulsatility matters. The pituitary somatotrophs release GH in discrete bursts. This episodic architecture exists partly to prevent receptor desensitization. Continuous GHRH exposure, as produced by CJC-1295 with DAC, can attenuate receptor responsiveness over time. The "recovery window", the period between stimulations during which the GHRH receptor resets, is largely eliminated with long-acting formulations.

Ipamorelin avoids this concern entirely. With a 2-hour half-life and activity at a different receptor family, it mimics a ghrelin pulse rather than a GHRH burst. Three daily injections spaced evenly preserve a near-physiological rhythm. Because Ipamorelin does not significantly raise cortisol or prolactin at standard doses, it is often described as a "clean" secretagogue from a side-effect standpoint.

For users running a no-DAC CJC-1295 and Ipamorelin combination, the practical goal is synchronized pulses: both agents administered together so that GHRH-receptor and ghrelin-receptor stimulation coincide at the somatotroph, maximizing GH output per injection event. More detail on whether Ipamorelin and CJC-1295 should be taken together covers the rationale for co-administration.

Tesamorelin occupies a unique position. Its pharmacokinetic profile is short, similar to no-DAC CJC-1295, but its clinical endpoints are measured over months. The compound was specifically developed to reduce visceral adipose tissue (VAT) in HIV-associated lipodystrophy, and trials demonstrated statistically significant VAT reduction at 26 and 52 weeks. That timeline means practitioners who start Tesamorelin and measure outcomes at four weeks are looking at the wrong interval entirely.

Exploring Tesamorelin benefits supported by clinical data provides context for what validated endpoints actually look like over appropriate timeframes.


Comparing Endpoints: IGF-1, Body Composition, and VAT Timing

Comparing Endpoints: IGF-1, Body Composition, and VAT Timing

Endpoint selection is where comparing GH secretagogues by exposure and endpoint timing becomes most actionable. Three primary readouts are used in practice:

1. GH Pulse Amplitude (sub-day)
Directly measures the GH spike after injection. Useful for pharmacodynamic confirmation but impractical for routine monitoring. Best matched to Ipamorelin or no-DAC CJC-1295 given their short windows.

2. Serum IGF-1 (weeks)
IGF-1 rises as cumulative GH exposure increases hepatic production. Meaningful elevation typically requires 4-8 weeks of consistent dosing. This is the appropriate intermediate biomarker for CJC-1295 and Ipamorelin stacks. A single fasted morning draw at week 6-8 is more informative than repeated early measurements.

3. Body Composition and VAT (months)
DEXA-measured lean mass changes and MRI-measured VAT reduction require 12-26 weeks minimum. These are the endpoints where Tesamorelin has the strongest evidence base. Using DEXA at 6 weeks to evaluate a CJC-1295/Ipamorelin stack is asking the measurement to detect a signal that has not yet developed.

"The most common error in secretagogue evaluation is measuring fast markers for slow endpoints, or slow markers for fast ones."

The regulatory picture reinforces Tesamorelin's status as the one compound in this group with an approved indication. The FDA-approved drug Egrifta targets VAT in a defined population, backed by randomized controlled trials. CJC-1295 and Ipamorelin rely on IGF-1 and body composition surrogates with smaller evidence bases, which does not invalidate their use, but means practitioners should calibrate expectations accordingly. For a direct mechanistic contrast, comparing Tesamorelin versus Sermorelin illustrates how endpoint data quality differs between secretagogue classes.

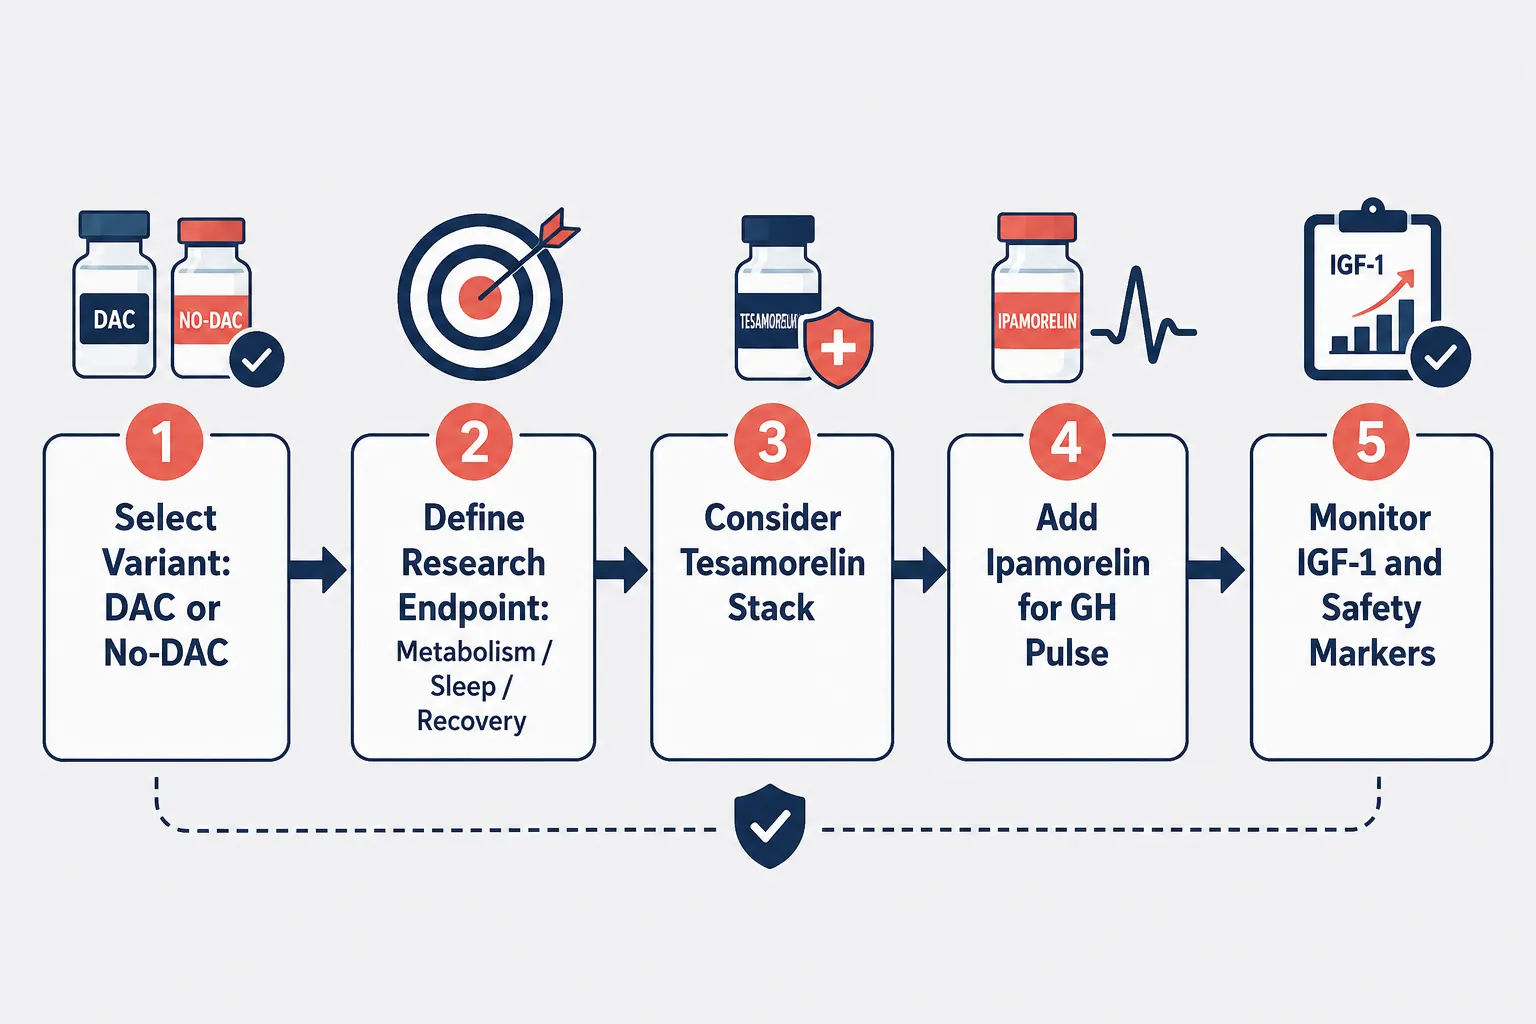
Practitioners who want a blend approach, combining Tesamorelin's VAT-focused mechanism with CJC-1295 and Ipamorelin's synergistic GH pulsatility, often look at formulations like the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend. In those contexts, endpoint timing still matters: IGF-1 is an appropriate 6-8 week marker, while VAT and body composition outcomes need a 3-6 month window.

For those exploring options with additional metabolic components, the Tesamorelin, AOD9604, CJC-1295, and Ipamorelin blend represents a broader approach, though each added agent also adds its own endpoint and measurement timing requirements.


Conclusion

Selecting among CJC-1295, Ipamorelin, and Tesamorelin is ultimately an exercise in matching three variables: the compound's exposure window, the receptor pathway engaged, and the endpoint's biological lag time. CJC-1295 with DAC offers sustained exposure but sacrifices pulse architecture. No-DAC CJC-1295 and Ipamorelin preserve pulsatility and are best evaluated via IGF-1 at 6-8 weeks. Tesamorelin's robust VAT evidence demands a 3-6 month evaluation horizon despite its short pharmacokinetic profile.

Actionable next steps:

  • Map your endpoint of interest (GH pulse amplitude, IGF-1, body composition, or VAT) to the appropriate measurement interval before starting a protocol.
  • Choose CJC-1295 without DAC over the DAC formulation when preserving pulsatility is a priority.
  • Co-administer Ipamorelin with no-DAC CJC-1295 in the same injection event to maximize synergistic GH pulse amplitude.
  • Set IGF-1 baseline before initiating any stack and retest no earlier than week 6.
  • Reserve VAT measurement for protocols that include Tesamorelin and allow a minimum 12-week window.
https://www.puretestedpeptides.com/wp-content/uploads/2026/10/cjc-1295-ipamorelin-and-tesamorelin-how-to-compare-gh-secretagogues-by-exposure.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-20 13:07:002026-10-20 13:07:00CJC-1295, Ipamorelin, and Tesamorelin: How to Compare GH Secretagogues by Exposure and Endpoint Timing
What Is a Diuretic? HCTZ, Furosemide, and Fluid-Balance Controls in GLP and Growth-Hormone Peptide Research

What Is a Diuretic? HCTZ, Furosemide, and Fluid-Balance Controls in GLP and Growth-Hormone Peptide Research

October 12, 2026/0 Comments/in Uncategorized/by

Fluid retention of just two liters can add more than four pounds to a subject's recorded body weight overnight, a shift large enough to mask or mimic a meaningful peptide-study endpoint. Understanding what a diuretic is, how agents like HCTZ and furosemide operate at the nephron level, and how GLP and growth-hormone peptides alter renal sodium handling is not a pharmacology footnote. It is a prerequisite for interpreting fluid-sensitive research data accurately.
Key Takeaways

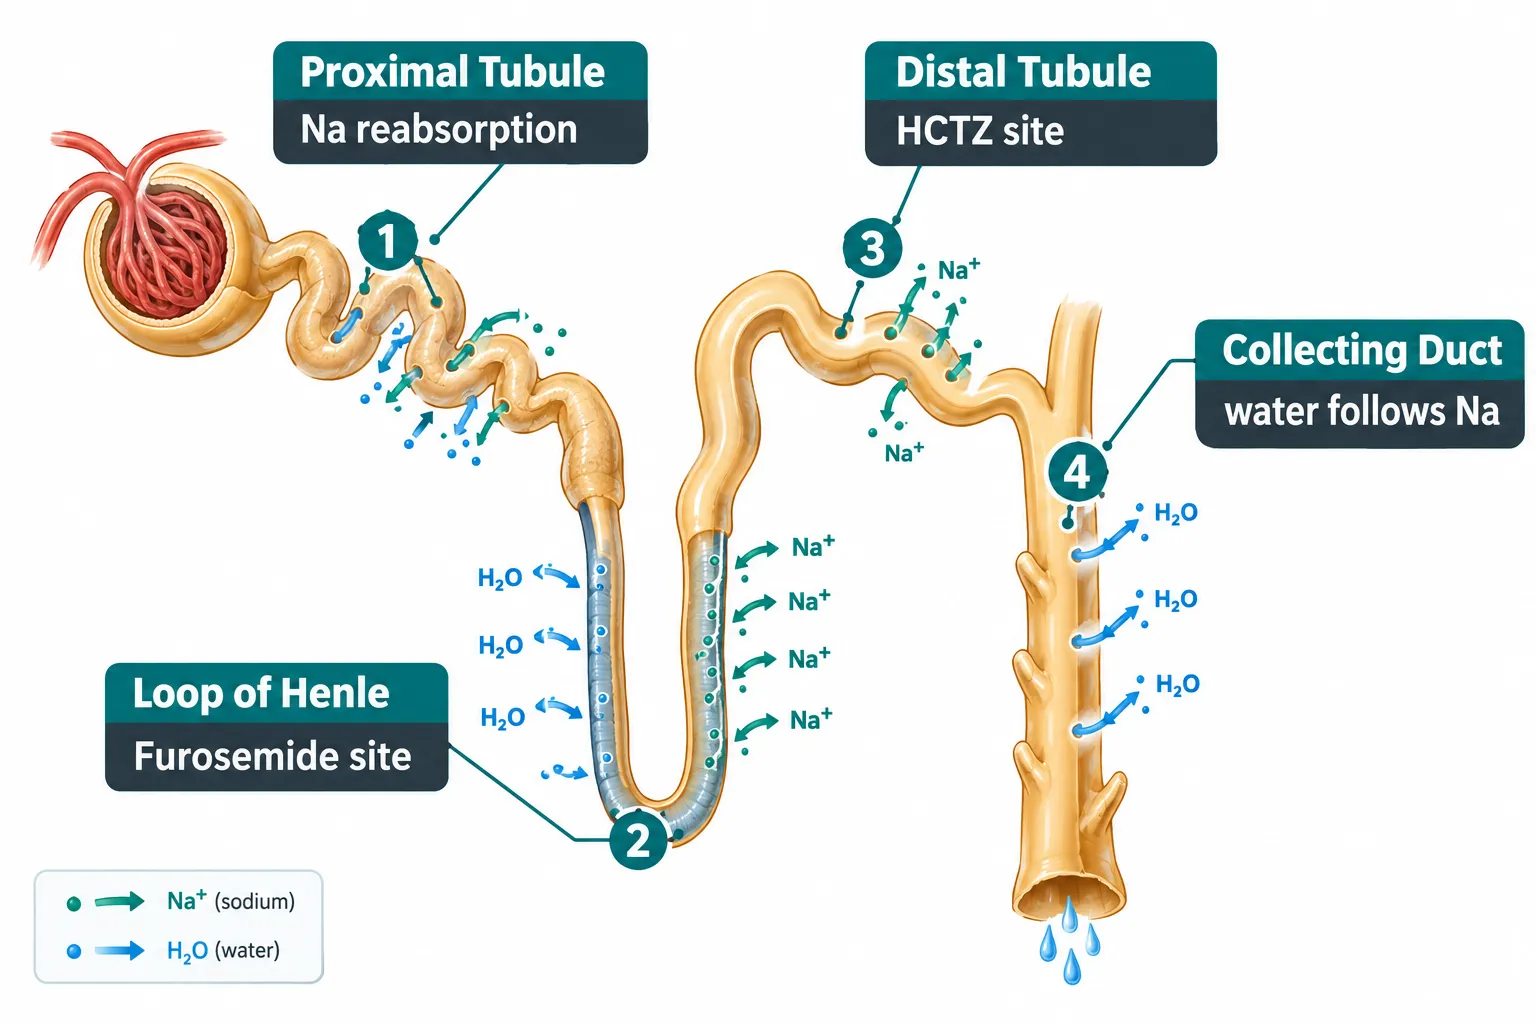
  • Diuretics increase urinary output by blocking sodium reabsorption at specific nephron sites; HCTZ acts on the distal tubule, furosemide on the loop of Henle.
  • GLP-1 receptor agonists carry intrinsic natriuretic properties that can reduce or offset diuretic requirements in research models.
  • Growth-hormone-related peptides reliably promote sodium and water retention, which can inflate body-weight readings and confound lean-mass endpoints.
  • Renal tubular sodium handling is the central "control knob" linking peptide pharmacology to plasma-volume and body-weight outcomes.
  • Researchers must account for diuretic use, hydration status, and peptide-driven fluid shifts when designing protocols and interpreting results.

Diuretics Defined: Mechanism, Classes, and the HCTZ vs. Furosemide Distinction

A diuretic is any agent that increases the rate of urine production by reducing renal tubular reabsorption of sodium and, consequently, water. Because water follows sodium osmotically, blocking sodium transport at any nephron segment pulls fluid into the tubular lumen and out of the body.

Diuretics Defined: Mechanism, Classes, and the HCTZ vs. Furosemide Distinction

The two agents most relevant to peptide research contexts are hydrochlorothiazide (HCTZ) and furosemide.

Feature HCTZ (Thiazide) Furosemide (Loop)
Site of action Distal convoluted tubule Thick ascending loop of Henle
Relative potency Moderate High ("high-ceiling")
Onset 1-2 hours 30-60 minutes (oral)
Primary use Hypertension, mild edema Acute heart failure, resistant edema
Electrolyte concern Hypokalemia, hyponatremia Hypokalemia, hypomagnesemia

HCTZ inhibits the Na-Cl cotransporter (NCC), producing a moderate, sustained diuresis well-suited to chronic fluid management. Furosemide inhibits the Na-K-2Cl cotransporter (NKCC2), delivering a rapid, powerful diuresis used when fluid overload is urgent or HCTZ-resistant.

A third class, potassium-sparing diuretics such as spironolactone, blocks aldosterone receptors in the collecting duct. These are less potent but preserve potassium, making them relevant when peptide protocols already stress electrolyte balance.


GLP-1 Peptides and Fluid Balance: Built-In Natriuretic Activity

GLP-1 receptor agonists (GLP-1 RAs) are among the most studied peptide classes in 2026 metabolic research. What is a diuretic effect in this context? Interestingly, GLP-1 RAs appear to generate one intrinsically.

Activation of GLP-1 receptors on renal proximal tubule cells inhibits the sodium-hydrogen exchanger (NHE3), reducing sodium reabsorption and promoting a mild but measurable natriuresis. This mechanism is distinct from classic diuretic pharmacology yet produces overlapping outcomes: lower plasma volume, reduced interstitial fluid, and modest decreases in body weight that are independent of fat loss.

"In some clinical observations, GLP-1 RA therapy has resolved diuretic-resistant fluid retention, a finding that underscores the direct renal activity of this peptide class."

For researchers studying GLP-1 peptides or the GLP-3R peptide, this intrinsic fluid-lowering activity creates a significant confound. A recorded drop in body weight during a GLP-1 RA protocol may reflect:

  • Reduced caloric intake (the intended endpoint)
  • Natriuresis-driven plasma-volume contraction
  • A combination of both

Separating these contributions requires baseline fluid-status assessment and, ideally, bioelectrical impedance or DEXA to distinguish fat mass from lean and water compartments.

Long-term data also suggest that GLP-1 RAs reduce heart-failure hospitalization rates, an outcome partly attributable to sustained natriuretic activity reducing cardiac preload. This means concurrent standard diuretic doses may need downward adjustment in research subjects already on GLP-1 RA protocols.


Growth-Hormone Peptides, Sodium Retention, and the Diuretic Counterbalance

Growth-Hormone Peptides, Sodium Retention, and the Diuretic Counterbalance

Where GLP-1 peptides tend to reduce fluid load, growth-hormone-related peptides reliably do the opposite. GH stimulates IGF-1 production, which in turn activates renal sodium reabsorption through multiple tubular pathways. The result is a well-documented pattern of sodium retention, plasma-volume expansion, and peripheral edema, particularly prominent in the first weeks of GH or GH-secretagogue administration.

Research involving sermorelin peptide or GHRP-2 vs. sermorelin comparisons must account for this fluid-retention phase. Early body-weight increases in GH-secretagogue protocols are frequently misread as lean-mass accrual when they largely represent water and sodium accumulation.

Updated 2026 analyses frame this fluid retention as a physiological "normalization" of extracellular volume in subjects who were previously GH-deficient, but the effect remains clinically significant and endpoint-distorting regardless of its origin.

Key fluid-related variables to track in GH-peptide protocols:

  • Morning body weight (fasted, post-void) at consistent intervals
  • Ankle circumference or pitting-edema assessment
  • Serum sodium and potassium at baseline and follow-up
  • Urine specific gravity as a hydration proxy

MK-677 (ibutamoren), an oral GH secretagogue, produces particularly notable fluid retention due to sustained GH and IGF-1 elevation. Researchers using this compound alongside AOD-9604, a GH fragment with a different receptor profile, should note that AOD-9604's fluid impact appears considerably lower, offering a useful within-protocol comparison point.
When edema is significant enough to require intervention, furosemide is typically preferred over HCTZ because of its faster onset and higher ceiling. However, aggressive loop diuresis in a GH-peptide protocol risks hypokalemia, which can itself alter cellular hydration and confound intracellular water measurements.


Fluid-Balance Controls as a Research Design Requirement

Fluid-Balance Controls as a Research Design Requirement

Treating diuresis as a passive background variable rather than an active experimental control is a common source of irreproducible peptide data. The convergence of GLP-1 natriuresis, GH-driven sodium retention, and standard diuretic pharmacology at the same renal tubular sites means that small differences in hydration protocol, diuretic timing, or sodium intake can shift body-weight readings by two to five pounds without any change in the variable of interest.

Practical controls for fluid-sensitive peptide research:

  1. Standardize sodium intake across the protocol period.
  2. Record diuretic use (type, dose, timing) as a tracked covariate, not an exclusion criterion.
  3. Use morning fasted body weight as the primary weight endpoint, not ad-hoc measurements.
  4. Separate body-composition assessment (lean mass, fat mass, total body water) from scale weight.
  5. Monitor serum electrolytes when combining GH-related peptides with any diuretic class.

For researchers exploring compounds such as cagrilinitide peptide, which combines GLP-1 and amylin receptor activity, the fluid picture becomes even more layered. Dual-agonist peptides may amplify natriuretic effects beyond those seen with single-receptor agents, making pre-protocol fluid-status documentation essential.

Similarly, mitochondria-targeted peptides like SS-31 are being studied in contexts involving oxidative stress and cellular energy, where systemic fluid shifts could alter tissue perfusion and confound outcome markers unrelated to the peptide's primary mechanism.

Looking forward, the expectation, speculative but plausible, is that researchers will increasingly co-administer low-dose potassium-sparing diuretics as a standardized fluid-control arm in GH-peptide trials, and that GLP-1 RA protocols will move toward explicit natriuresis measurement as a secondary endpoint rather than an uncontrolled variable.


Conclusion

Understanding what a diuretic is, and how HCTZ, furosemide, and renal sodium handling interact with GLP and growth-hormone peptide pharmacology, is foundational to producing reliable research data in 2026. The actionable steps are clear: document fluid status at baseline, track diuretic use as a covariate, separate scale weight from body composition, and select diuretic class based on the specific fluid-retention mechanism in play. Researchers who treat fluid balance as a controlled variable rather than background noise will produce endpoints that hold up to scrutiny and replication.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/what-is-a-diuretic-hctz-furosemide-and-fluid-balance-controls-in-glp-and-growth.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-12 13:06:342026-11-13 20:07:15What Is a Diuretic? HCTZ, Furosemide, and Fluid-Balance Controls in GLP and Growth-Hormone Peptide Research
CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation

CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation

September 25, 2026/0 Comments/in Uncategorized/by

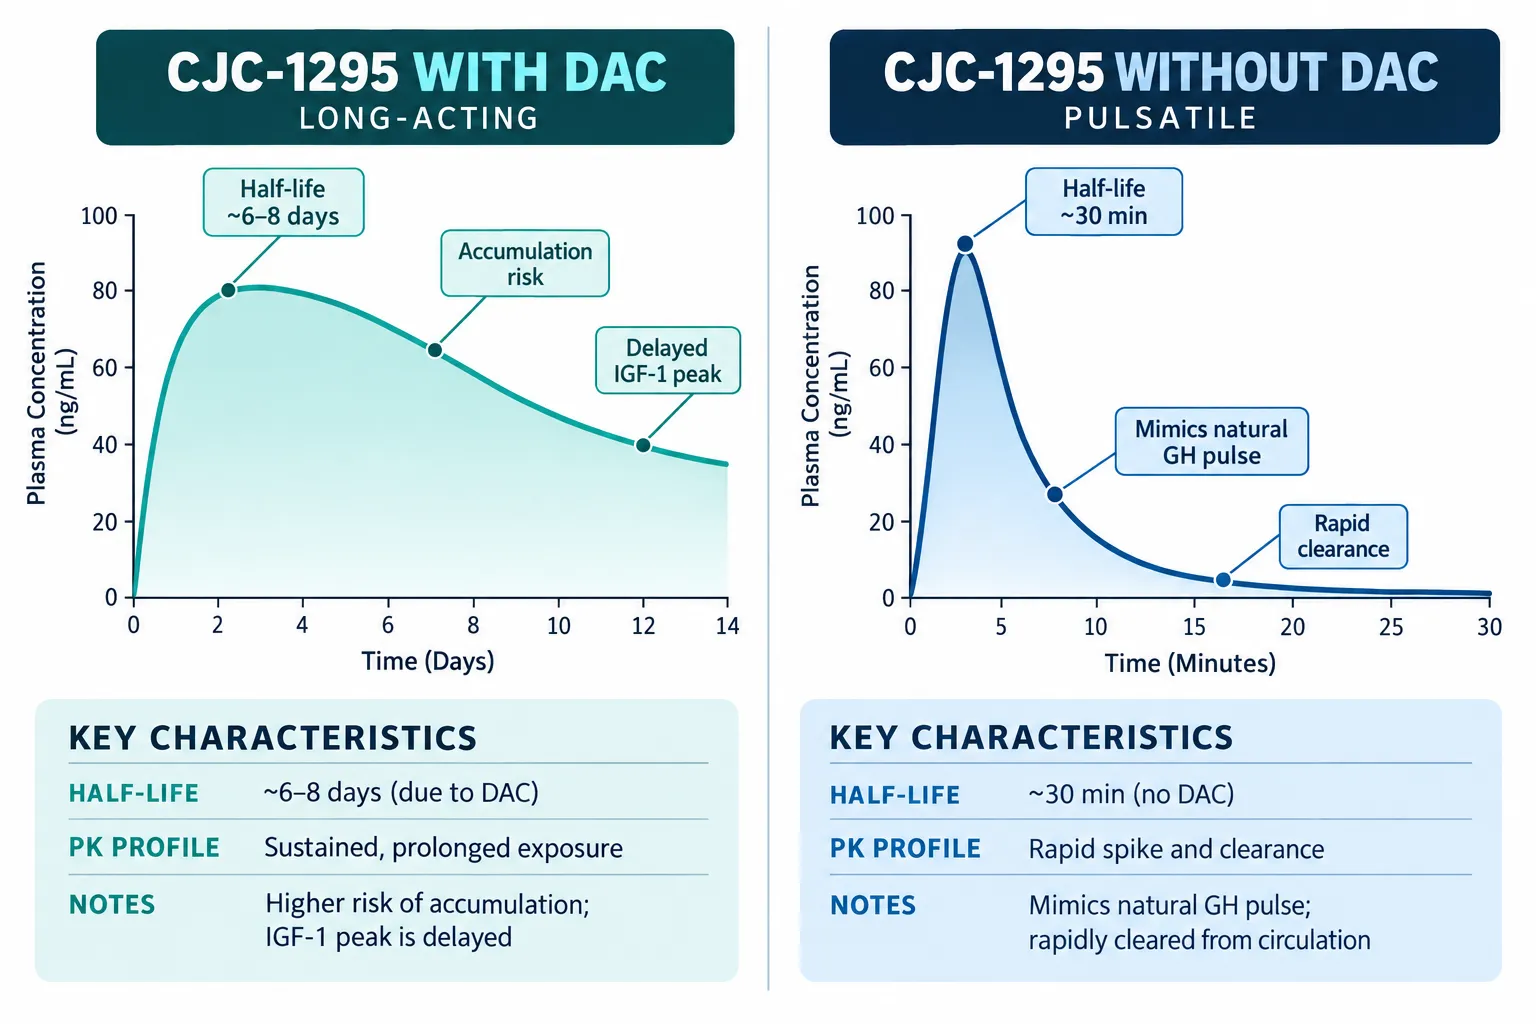
A single amino acid modification, the Drug Affinity Complex (DAC), extends CJC-1295's plasma half-life from roughly 30 minutes to approximately six to eight days. That difference is not merely pharmacokinetic trivia. It reshapes every decision a researcher makes: when to draw blood, how long to wait before the next treatment cycle, and whether an observed IGF-1 signal belongs to the compound or to residual accumulation from a prior dose. Understanding CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation is therefore foundational to producing reproducible, attributable preclinical data.

Key Takeaways

  • CJC-1295 without DAC has a half-life near 30 minutes, making it ideal for studying acute, pulsatile GH release; CJC-1295 with DAC sustains elevated GH and IGF-1 for days to weeks.
  • Sampling windows must be matched to the compound's kinetic profile, mismatched timing leads to missed peaks or inflated baseline readings.
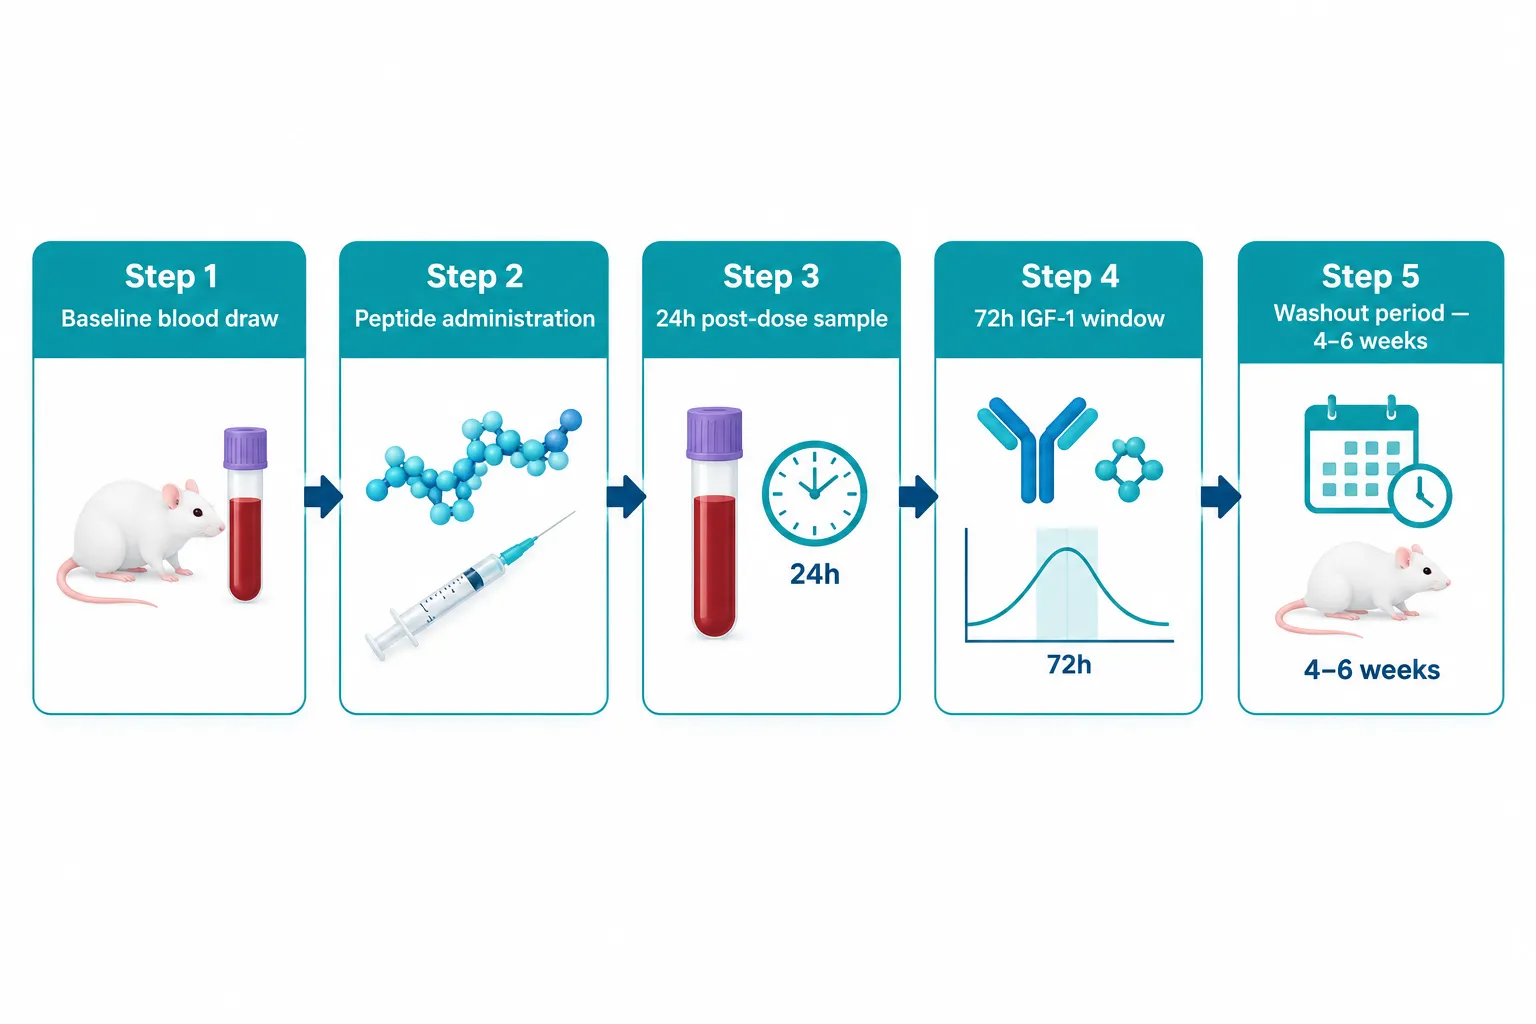
  • Washout for DAC-containing protocols requires a minimum of four to six weeks in rodent models to avoid carryover confounding.
  • IGF-1 attribution is the central interpretive challenge: sustained DAC exposure elevates tonic IGF-1, while the non-DAC form produces transient pulses that are easy to miss without frequent sampling.
  • Study design choices, dose interval, sample frequency, and washout length, differ substantially between the two forms and must be pre-specified in the protocol.

Half-Life Determines Everything Downstream

Half-Life Determines Everything Downstream

The pharmacokinetic contrast between the two forms is the logical starting point because every downstream design decision flows from it. CJC-1295 without DAC is a modified GHRH analogue that resists enzymatic cleavage long enough to reach pituitary receptors but is cleared within one to two hours in most rodent models. Its action is therefore discrete and pulse-like, closely mirroring endogenous GHRH activity.

CJC-1295 with DAC covalently binds to circulating albumin through its maleimido-propionyl group. This albumin linkage creates a depot effect, releasing active peptide slowly over days. In rat models, a single subcutaneous dose produces measurable GH elevation for up to five days and elevated IGF-1 for seven to ten days. The practical consequence is that a researcher who draws a single blood sample at 24 hours post-dose will capture very different biological states depending on which form was used.

For researchers exploring multi-peptide combinations, the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend illustrates how stacking long- and short-acting GHRH analogues complicates attribution further, reinforcing the need for precise kinetic mapping before interpreting outcomes.


Sampling Windows in Cell and Animal Studies: Matching Timing to Kinetics

Getting sampling windows right is where most preclinical CJC-1295 studies succeed or fail. The two forms demand fundamentally different schedules.

Without DAC: High-Frequency, Narrow Windows

Because the non-DAC form acts within minutes and clears rapidly, meaningful GH sampling must occur within 15 to 45 minutes post-administration in rodent models. A single time-point study will almost always underestimate peak GH. Recommended practice calls for serial sampling at 15, 30, 60, and 120 minutes to capture the full pulse shape. IGF-1, which responds more slowly to GH stimulation, should be sampled at 4, 8, and 24 hours to capture the downstream hepatic response.

Cell culture studies using the non-DAC form face an analogous challenge: peptide degradation in serum-containing media can reduce effective concentration within hours, so dosing intervals and media refresh schedules must be tightly controlled.

With DAC: Extended Windows, Accumulation Awareness

For the DAC form, single time-point sampling at 24 or 48 hours post-dose is more defensible, but researchers must account for accumulation across repeated doses. In a weekly dosing protocol over four weeks, plasma concentrations do not reach steady state until approximately the third dose. This means IGF-1 readings taken during weeks one and two reflect rising exposure, not steady-state biology. Comparing week-one IGF-1 to week-four IGF-1 without acknowledging this trajectory is a common interpretive error.

Recommended sampling in repeated-dose rodent studies with the DAC form:

  • Trough samples immediately before each dose (to track accumulation)
  • Peak samples 24 to 48 hours after each dose
  • IGF-1 at 72 hours post-dose, where the signal is most stable
  • A terminal bleed at least seven days after the final dose to distinguish residual compound from true washout baseline

For those working with related combination protocols, the Sermorelin, Ipamorelin, and CJC-1295 blend offers context on how multiple secretagogues interact when sampling schedules must account for overlapping kinetic profiles.


Washout Design and IGF-1 Interpretation

Washout Design and IGF-1 Interpretation

Washout is arguably the most underspecified element in published CJC-1295 animal studies. A compound with a six-to-eight-day half-life requires approximately five half-lives, roughly 30 to 40 days, to fall below 5% of peak plasma concentration. In practice, most expert guidance as of 2026 recommends a minimum four-to-six-week washout in rodent models before a crossover arm or a new treatment cycle begins.

Shorter washouts produce carryover elevation of IGF-1 that can be misattributed to a new intervention. This is particularly problematic in crossover designs where the DAC form is tested first.

Attributing GH Pulsatility vs. Sustained Elevation

The interpretive challenge is not just about timing, it is about biology. The non-DAC form preserves the pulsatile nature of GH secretion. Studies examining GH-dependent cellular processes such as lipolysis, protein synthesis, or IGF-1 receptor upregulation benefit from this pulsatility because it more closely models physiological signaling. The DAC form, by contrast, creates a tonic elevation that may saturate GH receptors and alter downstream sensitivity over time.

"Sustained GH elevation and pulsatile GH elevation are not interchangeable experimental conditions, they activate overlapping but distinct receptor dynamics."

Researchers must therefore specify in their protocols whether the biological question requires pulsatile or sustained GH exposure, and select the appropriate form accordingly. Mixing the two forms within a single study without a full washout between them produces data that cannot be cleanly attributed to either kinetic profile.

For additional context on how CJC-1295 is used alongside complementary peptides in research settings, the Tesamorelin, AOD9604, CJC-1295, and Ipamorelin 12mg blend page provides relevant formulation background. Similarly, researchers comparing secretagogue safety profiles may find the discussion on combining Tesamorelin with CJC Ipamorelin useful for contextualizing multi-compound study designs.


Practical Protocol Recommendations

Practical Protocol Recommendations

The following framework consolidates current best-practice guidance for preclinical researchers as of 2026:

Parameter Without DAC With DAC
GH sampling window 15-60 min post-dose 24-48 h post-dose
IGF-1 sampling window 4-24 h post-dose 48-72 h post-dose
Steady-state onset Single dose ~3rd dose (weekly protocol)
Minimum washout 48-72 hours 4-6 weeks
Crossover design risk Low High without full washout

For dose-ranging studies, the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend dosage guide and the corresponding dose reference offer practical starting points when CJC-1295 is part of a multi-peptide protocol.

Key protocol checkpoints:

  • Pre-specify whether the study question requires pulsatile or tonic GH exposure
  • Document accumulation phase separately from steady-state phase in multi-dose designs
  • Include a satellite group for washout verification if the study uses a crossover design
  • In cell studies, refresh media at intervals matched to the peptide's degradation rate in the specific media formulation used

Conclusion

The choice between CJC-1295 with DAC and without DAC is not simply a matter of dosing convenience, it is a fundamental experimental variable that determines when to sample, how long to wait, and how to interpret every GH or IGF-1 data point the study generates. Researchers who treat the two forms as interchangeable risk producing results that are either uninterpretable or actively misleading.

Actionable next steps for preclinical researchers:

  1. Define the biological question first, pulsatile or sustained GH exposure, then select the compound form that matches it.
  2. Build sampling schedules around the compound's actual kinetic profile, not convenience time-points.
  3. Enforce a minimum four-to-six-week washout for any DAC-containing protocol before a crossover or repeat cycle.
  4. Track trough concentrations across a multi-dose DAC study to confirm when steady state is reached before drawing mechanistic conclusions.
  5. Report the form used, the sampling schedule, and the washout length explicitly in methods sections so findings can be accurately compared across studies.

Rigorous attention to these design elements is what separates publishable, reproducible CJC-1295 research from data that raises more questions than it answers.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cjc-1295-with-dac-vs-without-dac-in-cell-and-animal-studies-sampling-windows-was.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-25 13:03:292026-11-13 20:06:29CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation
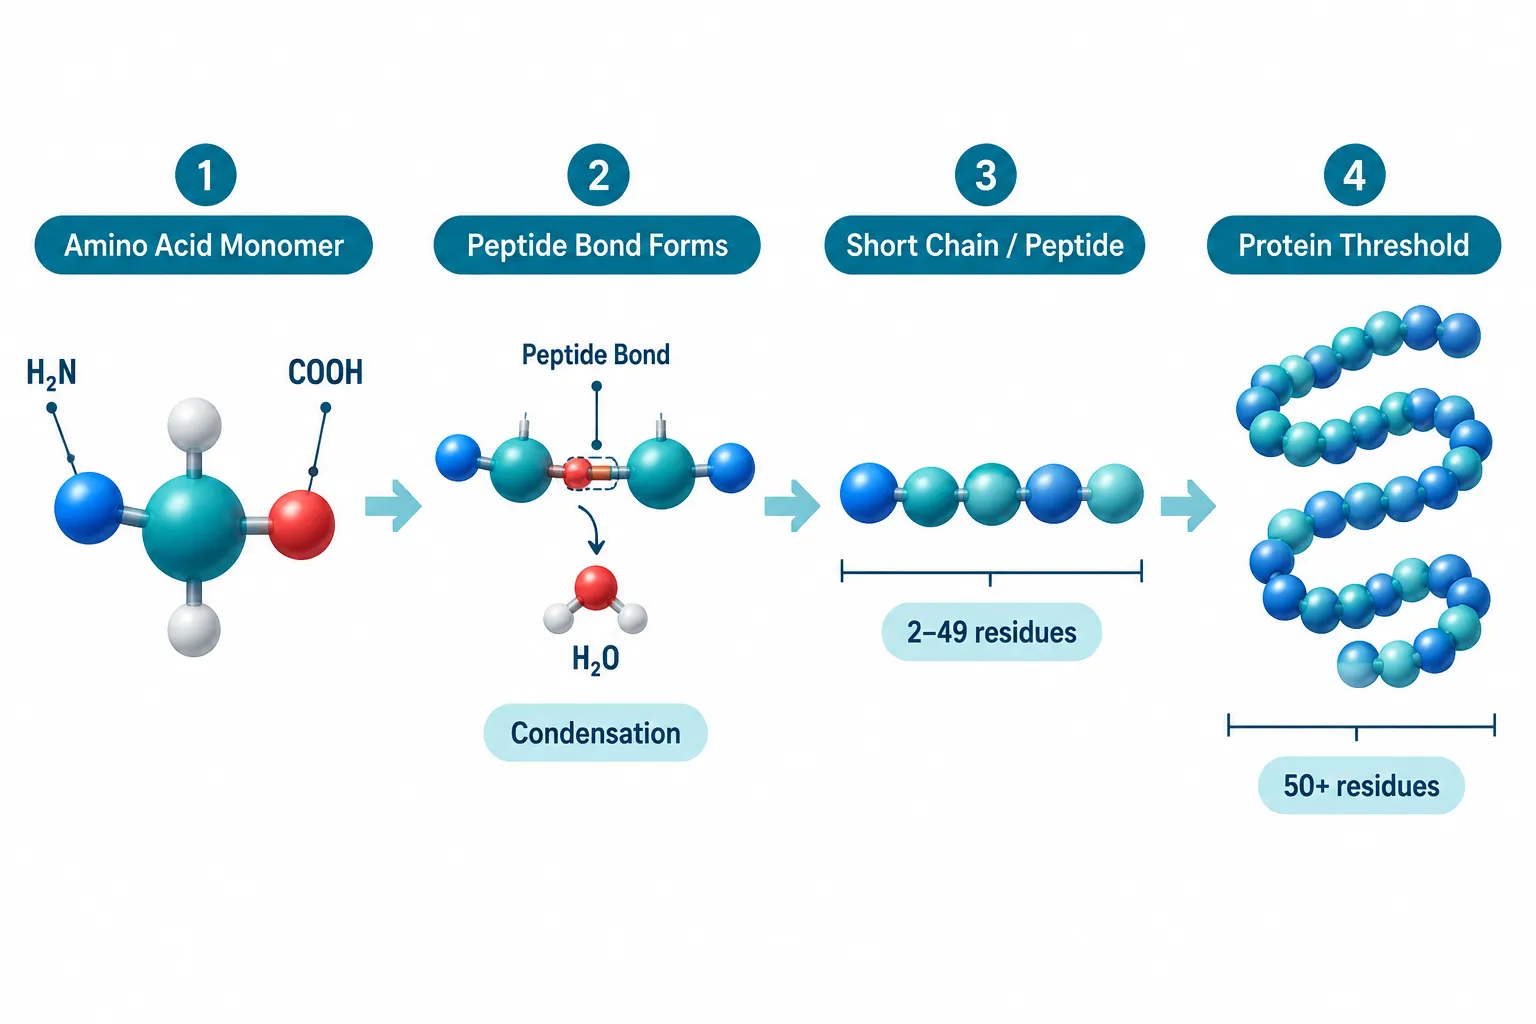
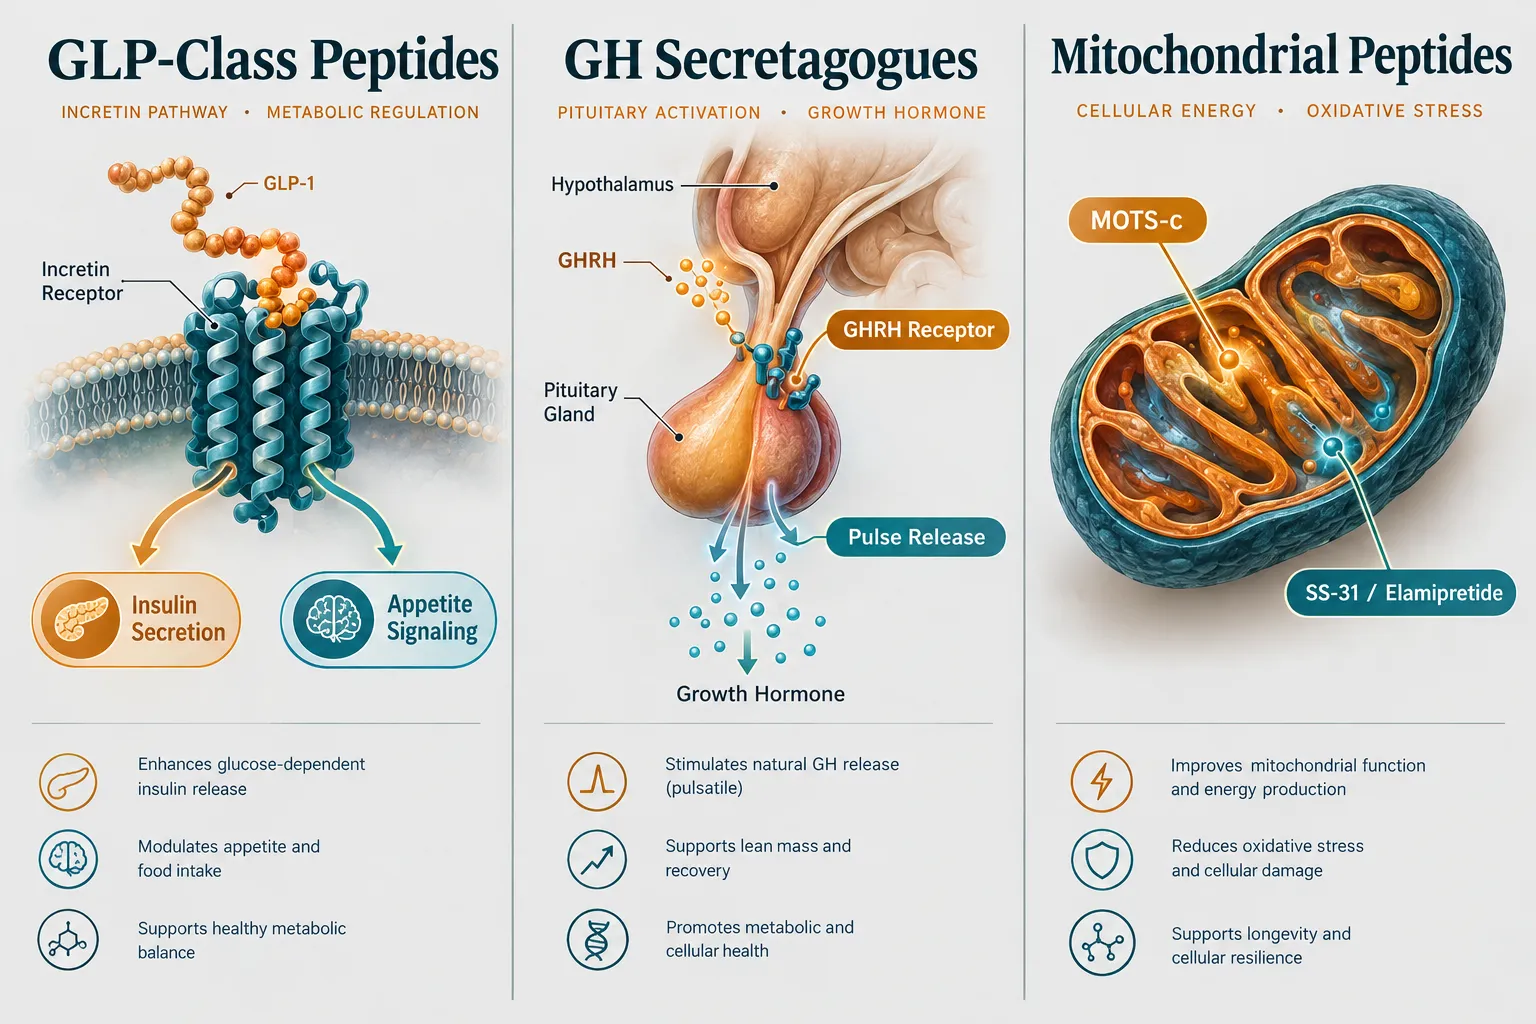
What Are Peptides? A Researcher’s Guide to Structure, Synthesis, and How GLP, Growth Hormone, and Mitochondrial Peptides Fit In

What Are Peptides? A Researcher’s Guide to Structure, Synthesis, and How GLP, Growth Hormone, and Mitochondrial Peptides Fit In

September 11, 2026/0 Comments/in Uncategorized/by

Over 100 peptide-based drugs have received regulatory approval worldwide, yet the term "peptide" remains loosely defined across research literature, lab catalogs, and popular science writing. For lab buyers and researchers selecting compounds in 2026, that ambiguity carries real consequences. Misclassifying a peptide class, conflating preclinical data with clinical evidence, or confusing research-grade compounds with approved therapeutics can derail study design before a single experiment begins.

This guide answers the foundational question, what are peptides?, and maps how GLP-class peptides, growth hormone secretagogues, and mitochondrial peptides each occupy a distinct corner of the research landscape.

Key Takeaways

  • Peptides are short chains of amino acids (typically 2-49 residues) that act as hormones, signaling molecules, and structural regulators throughout biology.
  • Peptide synthesis methods, especially solid-phase peptide synthesis (SPPS), allow researchers to engineer analogs with modified stability and receptor selectivity.
  • GLP-class peptides represent the most evidence-rich peptide category, with multiple approved drugs and active phase 3 trials.
  • Growth hormone secretagogue peptides show mechanistic promise but lack human randomized controlled trial data and regulatory approval.
  • Mitochondrial peptides such as SS-31 (elamipretide) have crossed the clinical threshold, while MOTS-c and humanin remain largely in preclinical development.

Peptide Structure: The Building Blocks Researchers Need to Understand

Amino acids are the alphabet of biology. Peptides are the short words, and proteins are the full sentences. When two or more amino acids link through a peptide bond, a covalent bond formed by condensation between the carboxyl group of one residue and the amino group of the next, the resulting chain is called a peptide.

Peptide Structure: The Building Blocks Researchers Need to Understand

The conventional boundary sits at roughly 50 amino acid residues. Chains below that threshold are peptides; chains above it are proteins. In practice, this line is not perfectly fixed, but it is a useful working definition for research purposes. Molecular weight typically falls below 5,000 daltons for most research peptides.

Why does size matter?

  • Smaller chains are easier to synthesize and modify in the lab.
  • They are more likely to be absorbed across biological membranes.
  • They degrade faster in biological systems, which affects study design.
  • Their receptor interactions tend to be more specific and easier to model computationally.

For a deeper look at how structure maps to function across peptide classes, the broad spectrum of peptides guide covering structure, synthesis, and research applications provides a thorough reference.

Synthesis and Engineering: How Research Peptides Are Made

The dominant laboratory method for producing research peptides is solid-phase peptide synthesis (SPPS), pioneered in the 1960s and refined continuously since. In SPPS, amino acids are added sequentially to a resin-bound chain, with protecting groups removed at each step. The final peptide is cleaved from the resin and purified, typically by high-performance liquid chromatography (HPLC).

Key synthesis concepts for lab buyers:

Term What It Means for Research
Purity (%) Percentage of the target peptide vs. impurities; 98%+ is standard for most research
Lyophilization Freeze-drying to extend shelf life and improve stability
Peptidomimetics Synthetic analogs designed to mimic peptide function with improved stability
Reconstitution Dissolving lyophilized peptide in bacteriostatic water or acetic acid before use

Beyond SPPS, researchers increasingly use recombinant biosynthesis for longer peptides and AI-assisted design to predict novel sequences with desired receptor affinity. These tools are accelerating the pace at which new research candidates enter preclinical pipelines.

For practical guidance on reconstitution and dosing calculations, the peptides calculator guide covering accurate dosing and reconstitution methods is a useful companion resource.

GLP, Growth Hormone, and Mitochondrial Peptides: Where Each Class Fits

This is where the researcher's guide to peptides becomes most actionable. The three classes below represent the highest research activity in 2026, yet they sit at very different points on the evidence continuum.

GLP, Growth Hormone, and Mitochondrial Peptides: Where Each Class Fits

GLP-Class Peptides: The Most Evidence-Rich Category

Glucagon-like peptides (GLP-1, GLP-2, and the triple-agonist GLP-3 class) are incretin hormones that regulate insulin secretion, gastric emptying, and appetite signaling. GLP-1 receptor agonists have multiple FDA-approved drugs and represent the strongest clinical evidence base in the peptide field.

Retatrutide, a GLP-1/GIP/glucagon triple agonist, is advancing through phase 3 trials and generating significant research interest around cardiometabolic and liver endpoints. Researchers studying this class should review the current research questions around GLP-3 peptides and what makes retatrutide different from other incretin analogs.

Growth Hormone Secretagogue Peptides: Mechanistic Promise, Evidence Gaps

Growth hormone-releasing peptides (GHRPs) and growth hormone-releasing hormone analogs such as CJC-1295 and ipamorelin stimulate pulsatile GH release through the GHRH receptor and ghrelin receptor pathways. Preclinical data on body composition, recovery, and metabolic parameters are compelling.

However: as of 2026, no GH secretagogue peptide has completed a human randomized controlled trial for the indications most commonly studied in research settings. None holds regulatory approval for those applications. Researchers should treat these compounds strictly as research tools.

For a mechanistic comparison of tesa and ipamorelin, the comparative analysis of tesa and ipamorelin mechanisms in growth hormone secretion research is a strong starting point. CJC-1295 formulation considerations are covered in the CJC-1295 with DAC half-life and dosing frequency research guide.

Mitochondrial Peptides: A Class at an Inflection Point

Mitochondrial-derived peptides (MDPs) are encoded within the mitochondrial genome and play roles in cellular energy regulation, stress response, and metabolic signaling. This class includes:

  • SS-31 (elamipretide / Forzinity): The first FDA-approved mitochondrial-targeted therapeutic, approved for Barth syndrome. This is a landmark in the MDP field.
  • MOTS-c: A mitochondrial-encoded peptide with strong preclinical signals in metabolic regulation, insulin sensitivity, and exercise response. Clinical development has been slower than early data suggested.
  • Humanin: Emerging preclinical data in kidney injury and neurodegeneration, but no clinical approvals.

The distinction between SS-31's approved status and the preclinical stage of MOTS-c matters enormously for research design. For a comparative review, see the best research peptides for mitochondrial function comparing MOTS-c and 5-Amino-1MQ.

Approved Peptide Drugs vs. Research Peptides: A Critical Distinction

Not all peptides in a lab catalog are equivalent in regulatory status. This table clarifies the landscape:

Category Examples Regulatory Status
Approved peptide drugs Semaglutide, elamipretide, insulin FDA/EMA approved for specific indications
Investigational peptides (clinical trials) Retatrutide Phase 2/3 trials; not yet approved
Research-use-only peptides MOTS-c, CJC-1295, ipamorelin Preclinical; no human approval
Tissue repair and signaling peptides GHK-Cu, BPC-157 Research use only

Research integrity depends on this distinction. Using a research-use-only compound outside a controlled research setting raises both scientific and regulatory concerns.

For tissue repair and skin matrix research, copper-binding peptides like GHK-Cu represent a separate functional class. The collagen signaling and copper peptides research covering GHK-Cu and skin models explores what researchers measure in that space.

Peptides in Oncology and Future Directions

Beyond metabolic and mitochondrial research, peptides are active in oncology as targeted delivery vehicles, receptor antagonists, and immune modulators. AI-driven peptide design is accelerating the identification of novel sequences with improved receptor selectivity and reduced off-target effects. In 2026, computational tools are shortening the gap between sequence design and preclinical validation.

Peptides in Oncology and Future Directions

The field is also expanding into nasal delivery formulations for neuropeptides, multi-peptide blends for tissue research, and polypeptide hormone analogs that interface with endocrine pathways. Researchers interested in how peptide signaling intersects with endocrine receptor biology can explore how serms interact with polypeptide hormones in research.

Conclusion

This researcher's guide to peptides, covering structure, synthesis, and how GLP, growth hormone, and mitochondrial peptides fit in, is designed to give lab buyers a reliable framework before selecting compounds. The actionable next steps are straightforward:

  1. Classify before you order. Identify whether the peptide of interest is approved, investigational, or research-use-only.
  2. Match synthesis quality to study requirements. Verify purity certificates, HPLC data, and mass spectrometry confirmation from vendors.
  3. Respect the evidence hierarchy. GLP-class peptides carry the strongest clinical data. GH secretagogues and most mitochondrial peptides do not.
  4. Design around the biology. Understanding peptide bond chemistry, receptor selectivity, and degradation pathways will produce more reproducible results.
  5. Stay current. The peptide research landscape in 2026 is moving fast, particularly in GLP-3 triple agonists and mitochondrial-targeted therapeutics.
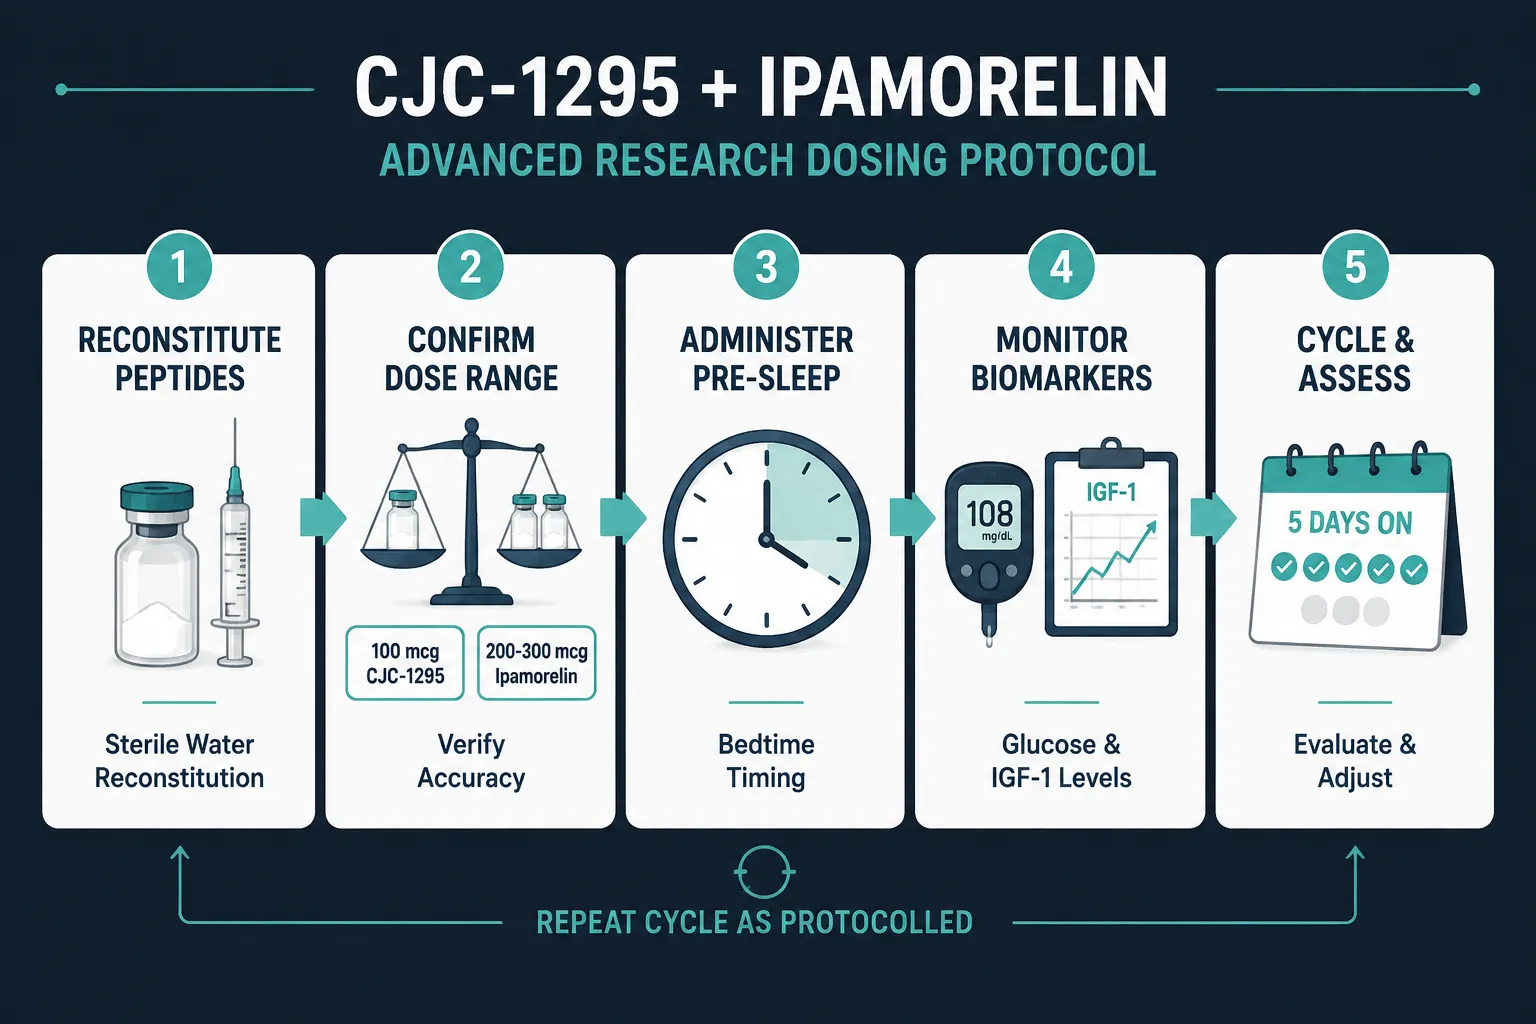
Researchers who ground their work in structural fundamentals and honest evidence assessment will be best positioned to extract meaningful data from this rapidly evolving field.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/what-are-peptides-a-researchers-guide-to-structure-synthesis-and-how-glp-growth.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-11 13:10:272026-09-11 13:10:27What Are Peptides? A Researcher’s Guide to Structure, Synthesis, and How GLP, Growth Hormone, and Mitochondrial Peptides Fit In
CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show

September 2, 2026/0 Comments/in Uncategorized/by

Growth hormone secretagogue research has quietly shifted gears. Where earlier studies focused almost exclusively on peak GH output, the conversation around CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show has expanded to include tissue recovery timelines, glucose-handling endpoints, and combination stacking strategies that were barely discussed five years ago. Researchers and clinicians in 2026 are asking more nuanced questions, not just "does IGF-1 rise?" but "what does that rise actually do in a metabolic or recovery context?"

Key Takeaways

  • CJC‑1295 with DAC offers a prolonged half-life suited to weekly dosing, while the no-DAC form aligns better with circadian-timed, daily micro-dose protocols.
  • Stacking CJC‑1295 with ipamorelin has become the dominant 2026 protocol pattern in both clinical and research settings.
  • IGF-1 elevation is well-documented, but hard endpoints for recovery and body composition remain limited in the published evidence base.
  • Desensitization risk with the DAC form makes structured washout periods a standard protocol feature in 2026 monographs.
  • Combination protocols now extend to Tesamorelin and metabolic peptides, broadening the research scope beyond classic GH modeling.

Understanding the Two Forms: DAC vs. No-DAC

Understanding the Two Forms: DAC vs. No-DAC

The core structural difference between the two variants drives nearly every protocol decision. CJC‑1295 with DAC (Drug Affinity Complex) binds to albumin in the bloodstream, dramatically extending its half-life to approximately eight days. This makes once-weekly or twice-monthly dosing pharmacologically feasible and reduces injection burden in longer research cycles.

CJC‑1295 without DAC, sometimes called Modified GRF(1-29), has a half-life of roughly 30 minutes. That short window is not a disadvantage in every context. Researchers exploring circadian-aligned dosing argue that brief, timed pulses more closely mimic the body's natural growth hormone release patterns, particularly when administered before sleep or around training windows.

Key pharmacokinetic comparison:

Feature With DAC Without DAC
Half-life ~8 days ~30 minutes
Dosing frequency Weekly or bi-weekly Daily or twice daily
GH pulse pattern Sustained elevation Acute, pulsatile
Desensitization risk Higher Lower
Protocol washout need Yes, structured Minimal

Desensitization is a genuine concern with the DAC form. Prolonged receptor stimulation can blunt pituitary responsiveness over time. Current somatotropin research protocols in 2026 address this by building in four-to-six-week washout periods after eight-to-twelve-week active cycles.

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show About Combination Stacking

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show About Com

The most significant protocol shift in 2026 is the near-universal pairing of CJC‑1295 with ipamorelin. Ipamorelin is a selective ghrelin receptor agonist that stimulates GH release through a complementary pathway. Together, the two peptides produce a synergistic GH pulse without the cortisol or prolactin elevation associated with older secretagogues.

"The combination of a GHRH analog with a selective ghrelin mimetic has become the reference stack in 2026 protocol literature, it amplifies the GH signal while keeping the hormonal side-effect profile narrow."

For researchers interested in this pairing, resources on sermorelin, ipamorelin, and CJC-1295 dosing provide useful context on how dosing ratios are being structured. A related product reference for lab-grade material is the CJC-1295 IPA 10mg formulation used in current research settings.

Beyond ipamorelin, 2026 protocols are increasingly incorporating Tesamorelin, an FDA-approved GHRH analog with a documented record from HIV lipodystrophy trials. That clinical history provides safety signals that pure research peptides lack. Researchers exploring this avenue can review the Tesamorelin and CJC-1295 combination framework, which positions both analogs within the broader GHRH class. Multi-peptide blends, such as those covered in Tesamorelin, CJC-1295, and ipamorelin 12mg blend protocols, are also appearing in emerging metabolic research designs.

Common 2026 stacking configurations:

  • CJC‑1295 (no DAC) + ipamorelin: nightly, circadian-timed
  • CJC‑1295 (with DAC) + ipamorelin: weekly CJC, daily ipamorelin
  • CJC‑1295 + Tesamorelin + ipamorelin: multi-target metabolic protocols
  • CJC‑1295 + AOD-9604 blends: body composition-focused research designs

What the Evidence Actually Shows, and Where It Falls Short

What the Evidence Actually Shows, and Where It Falls Short

Honest assessment of the evidence base matters here. IGF-1 elevation following CJC‑1295 administration is consistently documented across multiple study designs. That finding is robust. What remains less clear is the translation of that IGF-1 rise into hard clinical endpoints.

What is reasonably supported:

  • Dose-dependent increases in IGF-1 and GH
  • Improved lean mass markers in some body composition studies
  • Potential benefits in tissue recovery research contexts, particularly around collagen synthesis pathways
  • Modest improvements in sleep quality linked to nocturnal GH pulsatility

What remains speculative or under-studied:

  • Long-term glucose metabolism effects at fixed clinic doses vs. weight-based trial doses
  • Durability of body composition changes after cycle cessation
  • Comparative efficacy of DAC vs. no-DAC forms on recovery-specific endpoints
  • Safety profile in populations beyond healthy adults and HIV lipodystrophy patients

The gap between weight-based dosing used in clinical trials and the fixed doses common in clinic or biohacking settings is a persistent methodological problem. Most trial data comes from weight-adjusted protocols; most real-world use does not follow that model. Researchers tracking tissue repair research outcomes need to account for this discrepancy when interpreting results.

Lab-based monitoring, specifically IGF-1, fasting glucose, and HbA1c panels, is now considered standard practice in responsible 2026 protocol designs, particularly for cycles exceeding eight weeks.

Conclusion

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show points toward a maturing field that is moving beyond simple GH elevation as a goal. The DAC form suits sustained, low-frequency dosing with structured washout; the no-DAC form fits circadian-aligned, pulsatile strategies. Combination stacking with ipamorelin and Tesamorelin is now the research norm rather than the exception.

Actionable next steps for researchers and clinicians:

  1. Select the CJC‑1295 variant based on dosing frequency needs and desensitization tolerance, not convenience alone.
  2. Pair with ipamorelin for synergistic GH pulse amplification with a cleaner hormonal side-effect profile.
  3. Establish baseline IGF-1, fasting glucose, and HbA1c before any cycle begins.
  4. Build washout periods into DAC-based protocols, typically four to six weeks after an eight-to-twelve-week active phase.
  5. Interpret body composition and recovery outcomes against trial-dosing literature with appropriate caution given the fixed-dose gap.

The evidence base will sharpen as more combination protocols generate structured outcome data. Until then, disciplined lab monitoring and conservative cycle design remain the most defensible approach.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cjc-1295-with-and-without-dac-in-emerging-recovery-and-metabolic-research-what-2-1.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-02 13:04:042026-11-13 20:06:29CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show
CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models

CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models

August 29, 2026/0 Comments/in Uncategorized/by

Fewer than a dozen peer-reviewed human trials have examined CJC‑1295 in any form since its synthesis, yet community dosing protocols for metabolic optimization and injury recovery have multiplied rapidly. That gap between widespread use and thin clinical evidence is exactly what makes CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models one of the most pressing topics in peptide science heading into 2026.

Key Takeaways

  • CJC‑1295 with DAC has a confirmed extended half-life of roughly six to eight days; the without-DAC variant acts in minutes and is largely uncharacterized in peer-reviewed human literature.
  • Growth hormone and IGF‑1 response data exist primarily for the DAC form; metabolic, body-composition, and recovery outcomes remain evidence gaps for both variants.
  • Community dosing for recovery and metabolism is protocol-driven, not evidence-driven, creating meaningful safety unknowns.
  • Stacking CJC‑1295 with Tesamorelin or Ipamorelin is a growing research model, but formal combination trial data are absent.
  • Regulatory and compounding restrictions tightened between 2023 and 2026, making purity verification a critical step for any research application.

The Pharmacokinetic Foundation: DAC vs. Without DAC

The Pharmacokinetic Foundation: DAC vs. Without DAC

Understanding CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models begins with the chemistry that separates the two variants.

CJC‑1295 with DAC incorporates a Drug Affinity Complex, a chemical modification that allows the peptide to bind reversibly to serum albumin. This binding dramatically extends its half-life to approximately six to eight days, producing a sustained elevation of growth hormone-releasing hormone (GHRH) activity. The result is a prolonged, blunted GH pulse that differs significantly from the body's natural pulsatile secretion pattern.

CJC‑1295 without DAC (sometimes called Modified GRF 1-29 or Mod GRF) lacks that albumin-binding modification. Its half-life is roughly 30 minutes, making it far more aligned with physiologic GHRH signaling. This shorter window is precisely why researchers and practitioners pair it with a GHRP such as Ipamorelin, to amplify a single, timed GH pulse.

Feature With DAC Without DAC
Half-life ~6-8 days ~30 minutes
GH pulse pattern Sustained, blunted Pulsatile, physiologic
Human trial data Limited but present Essentially absent
Peer-reviewed metabolic data Minimal Near zero

For a deeper look at why half-life differences matter in research design, see CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research.

Metabolic and Body-Composition Research: Where the Evidence Stands

Metabolic and Body-Composition Research: Where the Evidence Stands

Most published data on CJC‑1295 focus narrowly on GH and IGF‑1 elevation. The metabolic story, lipolysis, insulin sensitivity, visceral fat reduction, and lean mass accrual, is far less developed.

What is reasonably supported:

  • Elevated IGF‑1 is associated with improved nitrogen retention and lean tissue support in multiple GH-axis studies, though not specifically attributed to CJC‑1295 without DAC in controlled trials.
  • The DAC form has shown statistically significant IGF‑1 elevation lasting up to 28 days in early human dose-escalation work.
  • Tesamorelin, a distinct GHRH analog with an FDA-approved indication for HIV-associated lipodystrophy, provides the closest proxy for what sustained GHRH stimulation can do to visceral adipose tissue. Researchers comparing these agents should review Ipamorelin vs Tesamorelin for mechanistic context.

What remains speculative:

  • Direct fat-loss outcomes attributable to CJC‑1295 without DAC in healthy subjects.
  • Sleep quality improvements, often cited in community forums, have no controlled human data linking them specifically to either CJC‑1295 variant.
  • Insulin sensitivity modulation, plausible given GH's known effects on glucose metabolism, but unstudied for this peptide directly.

"The absence of evidence is not evidence of absence, but in a regulatory and safety context, it functions as one until trials are conducted."

Recovery Models, Stacking Protocols, and the Evidence Gap

Recovery Models, Stacking Protocols, and the Evidence Gap

Injury recovery is perhaps the most enthusiastically discussed application of CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models, and the one with the least formal support.

The theoretical basis is coherent. GH and IGF‑1 both play established roles in collagen synthesis, satellite cell activation, and connective tissue repair. If CJC‑1295 reliably elevates these signals, downstream recovery benefits are biologically plausible. The problem is the inferential leap from plausibility to protocol.

Stacking With Tesamorelin and Ipamorelin

A growing number of research models combine CJC‑1295 without DAC with either Tesamorelin or Ipamorelin to target complementary points on the GH axis. Multi-peptide blends designed for this purpose are available for research use, for example, formulations such as the Tesamorelin, AOD9604, CJC-1295, Ipamorelin 12mg blend represent how researchers are structuring combination protocols in 2026.

Key considerations for combination research models:

  • Receptor saturation: Stacking a GHRH analog with a GHRP creates synergistic GH release, but the ceiling effect and desensitization timeline are not well-mapped.
  • IGF‑1 overshoot risk: Sustained supraphysiologic IGF‑1 carries theoretical oncogenic and insulin-resistance concerns that no long-term CJC‑1295 trial has adequately addressed.
  • Protocol standardization: Community dosing is largely reverse-engineered from Tesamorelin clinical data. Researchers using Tesamorelin and CJC-1295 Ipamorelin 12mg blend formulations should treat dosing guidance as investigational, not clinical.

Regulatory and Purity Context in 2026

The FDA's tightened compounding restrictions between 2023 and 2026 have directly affected the availability and sourcing landscape for both CJC‑1295 variants. For any preclinical or in-vitro research application, purity verification through third-party Certificate of Analysis (CoA) documentation is non-negotiable. Resources on peptide CoA verification and high-purity peptide sourcing provide practical guidance for maintaining research integrity.

The clinical development program for CJC‑1295 was halted before Phase III completion, meaning no modern large-scale trial data exist. Sports and performance-enhancement literature in 2026 continues to flag both variants as prohibited substances under WADA rules, reinforcing their strictly investigational status.

Conclusion

CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models represents a field where biological plausibility has raced far ahead of controlled evidence. The pharmacokinetic distinction between the two variants is well-established; the metabolic, recovery, and sleep-related outcomes that dominate community discussion are not.

Actionable next steps for researchers and informed readers:

  1. Distinguish the variants clearly before designing any protocol, half-life differences make the two compounds functionally distinct research tools.
  2. Anchor expectations to Tesamorelin data when evaluating metabolic claims, as it provides the closest evidence-based proxy for GHRH analog effects on body composition.
  3. Prioritize purity verification, regulatory tightening in 2026 makes sourcing integrity a first-order concern, not an afterthought.
  4. Treat stacking protocols as hypothesis-generating, not validated, combination models with Ipamorelin or Tesamorelin are promising research directions, not proven therapies.
  5. Monitor the clinical trial landscape, the absence of modern Phase II/III data for either variant is the single largest obstacle to evidence-based application.

The questions surrounding CJC‑1295 beyond GH elevation are worth asking. Answering them rigorously will require the kind of controlled human research that, as of 2026, has yet to arrive.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-and-without-dac-beyond-growth-hormone-emerging-questions-in-metabo.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-29 13:09:222026-08-29 13:09:22CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models
CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Advanced Research Protocols

CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Advanced Research Protocols

August 23, 2026/0 Comments/in Uncategorized/by

Growth hormone secretion declines by roughly 14% per decade after age 30, a physiological reality that has driven intense scientific interest in peptide-based strategies to restore pulsatile GH dynamics. Among the combinations studied in research settings, CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Advanced Research Protocols has emerged as one of the most discussed dual-mechanism stacks in endocrine peptide science. By targeting two distinct receptor pathways simultaneously, this pairing offers a mechanistically rational approach to amplifying the body's own GH pulses rather than replacing them with exogenous hormone.

Key Takeaways

  • CJC-1295 acts at the GHRH receptor to extend GH pulse amplitude, while Ipamorelin activates the GHS-R1a ghrelin receptor to initiate discrete GH pulses, creating a complementary synergy.
  • Combined use is reported to produce 3- to 5-fold increases in GH pulse amplitude compared to either peptide alone, based on extrapolated single-agent data and clinic-level observations.
  • No randomized controlled human trials have specifically tested the CJC-1295/Ipamorelin stack; the evidence base relies on single-agent studies and observational protocols.
  • Neither peptide is FDA-approved, and both remain in a complex regulatory environment regarding compounding status as of 2026.
  • Advanced research protocols must include rigorous monitoring of glucose metabolism, cardiovascular markers, and injection-site reactions.

Mechanistic Synergy: How the Dual-Pathway Design Works

The scientific rationale behind CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Advanced Research Protocols begins at the receptor level. CJC-1295 is a synthetic analog of growth hormone-releasing hormone (GHRH). It binds to GHRH receptors on pituitary somatotroph cells, stimulating them to release GH in larger, more sustained pulses. The Drug Affinity Complex (DAC) modification extends its half-life considerably, while the no-DAC version produces a shorter, more physiologic burst.

Mechanistic Synergy: How the Dual-Pathway Design Works

Ipamorelin, by contrast, is a selective growth hormone secretagogue (GHS) and ghrelin receptor agonist. It binds to the GHS-R1a receptor, triggering a separate but complementary cascade that initiates discrete GH pulses. Critically, Ipamorelin does not significantly elevate cortisol or prolactin at research-relevant doses, making it one of the more selective agents in its class.

When both peptides are administered together, they engage two independent signaling pathways that converge on the same output: pituitary GH release. This is not simple addition. The GHRH pathway primes somatotrophs and amplifies pulse height, while the ghrelin-receptor pathway provides the triggering signal. Extrapolation from separate single-agent trials and clinic-level data suggests the combination can produce GH pulse amplitudes 3 to 5 times above baseline, a magnitude that neither peptide achieves alone.

Researchers interested in exploring the broader landscape of hormone research protocols will find this dual-receptor model a useful framework for understanding how stacked peptides differ from single-agent approaches.

Advanced Research Protocol Design and Dosing Considerations

Designing a rigorous protocol around CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Advanced Research Protocols requires careful attention to formulation choice, timing, and dose selection.

Formulation options:

Variant Half-Life Typical Research Dose Frequency
CJC-1295 (no DAC) ~30 minutes 100 mcg Once or twice daily
CJC-1295 with DAC ~6-8 days 1-2 mg Weekly
Ipamorelin ~2 hours 200-300 mcg 1-3 times daily

Contemporary protocol guides describe a common starting point of approximately 0.2 mg of a combined CJC-1295/Ipamorelin injection per administration, with titration guided by subject age, body weight, and tolerability. An FDA docket document reviewing this combination references example blend concentrations of 1-2 mg/mL of each peptide, with 0.05-0.1 mL administered at bedtime, five nights per week, as a representative advanced research schedule.

Timing matters. GH is naturally secreted in pulses, with the largest pulse occurring in early slow-wave sleep. Administering the stack at bedtime aligns with this physiological rhythm and avoids blunting the natural pulse through competitive feedback.

Researchers comparing this stack against single-agent secretagogues may also find value in reviewing the Sermorelin vs CJC-1295 comparison and the Ipamorelin and Sermorelin stack research to contextualize where this combination sits within the broader GHRH-analog landscape.

For researchers evaluating pre-blended options, the CJC-1295 IPA 10mg product and detailed guidance on CJC-1295/Ipamorelin dosage protocols offer additional reference points for protocol calibration.

Advanced Research Protocol Design and Dosing Considerations

Key research design principle: Pulsatile administration that mirrors endogenous GH secretion rhythms produces more physiologically relevant data than continuous infusion models.

Safety Profile, Regulatory Status, and Research Boundaries

No discussion of CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Advanced Research Protocols is complete without a thorough review of the safety and regulatory context.

Commonly reported adverse effects in research subjects include:

  • Flushing, headache, and transient dizziness
  • Increased heart rate and mild body temperature elevation
  • Injection-site irritation or redness
  • Transient fluid retention (tingling in hands, mild edema)
  • Sleep changes, including vivid dreams or drowsiness
  • Joint discomfort or mild musculoskeletal effects

More serious risks identified in regulatory and safety reviews include immunogenic reactions (including rare anaphylaxis), insulin resistance with sustained IGF-1 elevation, and documented serious adverse events associated with intravenous administration of Ipamorelin in non-GH indications.

Regulatory status as of 2026 remains complex. Both peptides were placed on the FDA 503A Category 2 bulk substances list, indicating they "may present significant safety risks" and cannot be legally compounded under Section 503A pending further review. As of mid-2026, no formal FDA reclassification has been published, and neither peptide appears on the Pharmacy Compounding Advisory Committee docket for 2026-2027. Industry speculation about reclassification following a February 2026 HHS announcement has not been confirmed by formal regulatory action.

Neither CJC-1295 nor Ipamorelin is FDA-approved for any indication, and no approved finished drug product combining them exists. All research use must operate within ethically approved, controlled study frameworks.

Endocrine and evidence-based medicine experts consistently recommend against use in subjects with cancer history, uncontrolled diabetes, significant cardiovascular disease, untreated sleep apnea, or during pregnancy and breastfeeding. Researchers designing studies involving related multi-peptide stacks may also consult resources on combining Tesamorelin with CJC-1295 and Ipamorelin blends and the safety considerations for combining Tesamorelin with CJC Ipamorelin for comparative protocol design.

Safety Profile, Regulatory Status, and Research Boundaries

Conclusion

The scientific case for CJC-1295 paired with Ipamorelin rests on a well-defined dual-receptor mechanism, a growing body of single-agent evidence, and clinic-level observational data suggesting meaningful GH pulse amplification. However, the absence of randomized controlled combination trials, unresolved regulatory status, and an incomplete long-term safety profile mean that this stack belongs firmly in the domain of advanced, controlled research, not routine clinical application.

Actionable next steps for researchers:

  1. Design ethically approved protocols that include pre-specified monitoring of fasting glucose, IGF-1 levels, cardiovascular markers, and injection-site reactions at defined intervals.
  2. Select formulation and timing carefully, no-DAC CJC-1295 with bedtime Ipamorelin administration aligns most closely with physiologic GH pulsatility.
  3. Track regulatory developments through official FDA channels, as the compounding status of both peptides may change without broad advance notice.
  4. Compare against related stacks using published single-agent data to contextualize findings within the broader GHRH-secretagogue literature.
  5. Restrict use to qualified research settings with appropriate institutional oversight and subject safety protocols.

The mechanistic elegance of this combination makes it a compelling subject for endocrine research. Responsible advancement of that research depends on rigorous protocol design, honest appraisal of the current evidence gaps, and strict adherence to evolving regulatory requirements.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-ipamorelin-optimizing-growth-hormone-release-for-advanced-research.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-23 13:04:012026-11-13 20:05:45CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Advanced Research Protocols
Page 1 of 212
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout
  • About
  • Contact
  • COA / Lab Testing
  • Shipping Policy
  • Terms and Conditions
  • Research Use Disclaimer

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top