Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: igf-1

CJC-1295 Without DAC vs. Tesamorelin: Pulsatile Growth Hormone Secretion Amplitude and Half-Life Metrics

CJC-1295 Without DAC vs. Tesamorelin: Pulsatile Growth Hormone Secretion Amplitude and Half-Life Metrics

October 30, 2026/0 Comments/in Uncategorized/by

Growth hormone (GH) does not flow steadily through the bloodstream, it fires in discrete pulses, and the amplitude of those pulses determines much of its biological potency. When researchers compare CJC-1295 Without DAC vs. Tesamorelin: Pulsatile Growth Hormone Secretion Amplitude and Half-Life Metrics, the central question is not simply which peptide raises GH levels, but how each one shapes the pulse itself, its height, its duration, and the downstream IGF-1 signal it leaves behind.

Key Takeaways

  • Tesamorelin has a documented plasma half-life of roughly 8 to 38 minutes depending on dosing schedule, yet reliably increases GH pulse amplitude and mean GH without adding extra pulses.
  • CJC-1295 Without DAC carries an estimated plasma half-life of approximately 30 minutes (sometimes cited up to 2 hours), producing sharp, short-lived GH bursts that closely mimic physiological secretion.
  • No published head-to-head clinical trial directly compares the two peptides on GH pulse amplitude or IGF-1 output under identical conditions.
  • Tesamorelin's pharmacokinetic data are FDA-validated; CJC-1295 Without DAC data come primarily from preclinical and observational research sources.
  • Combination protocols pairing either peptide with a GH secretagogue such as ipamorelin are commonly explored to refine pulse timing and amplitude in research models.

Understanding the Pharmacokinetic Framework
Understanding the Pharmacokinetic Framework

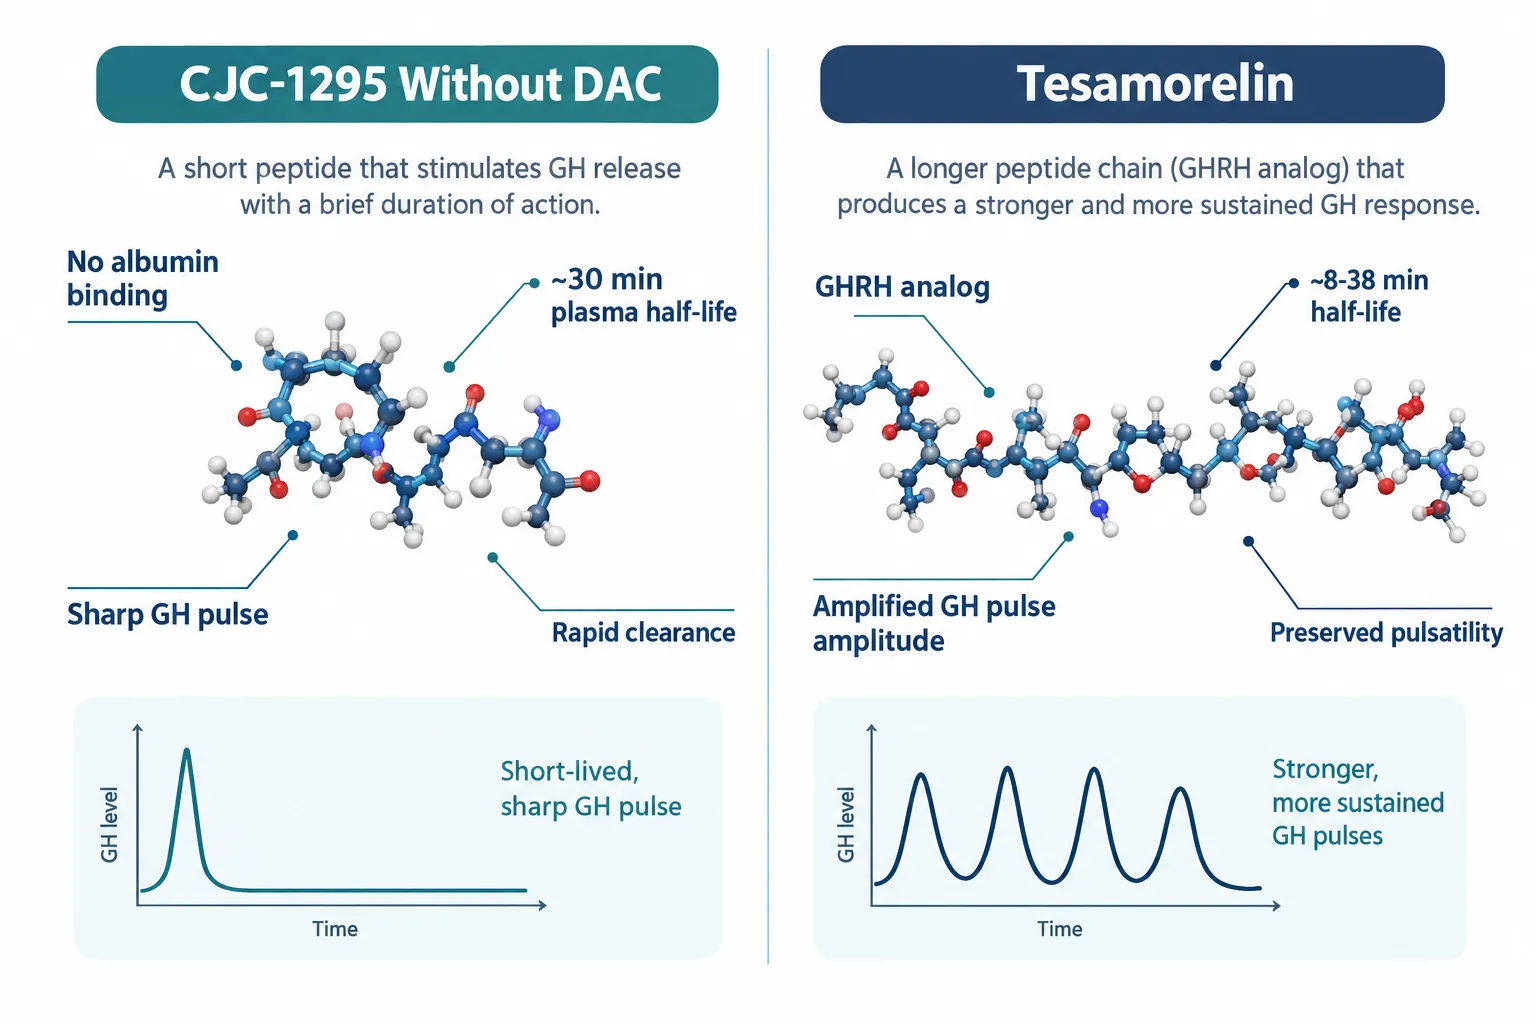
Before placing these two peptides side by side in a comparative protocol, it helps to understand what "half-life" actually measures in this context. Plasma half-life reflects how quickly a peptide is cleared from circulation, but a short plasma half-life does not mean a short biological effect. Both tesa and CJC-1295 Without DAC demonstrate this disconnect clearly.

Tesamorelin is a synthetic analog of endogenous growth hormone-releasing hormone (GHRH). Its plasma half-life after a single subcutaneous dose sits between approximately 8 and 13 minutes; with repeated daily dosing, that figure extends to roughly 26 to 38 minutes. Despite this brief window of systemic exposure, once-daily injections are sufficient to amplify nocturnal GH pulses and produce a sustained rise in IGF-1 measured between doses. The peptide achieves this by binding GHRH receptors in the pituitary with high affinity, triggering a sharp intracellular cascade that outlasts its own presence in plasma.

CJC-1295 Without DAC (also written as Modified GRF 1-29) lacks the drug-affinity complex (DAC) that tethers its longer-acting counterpart to albumin. Without albumin binding, the peptide is cleared relatively fast, estimated plasma half-life of around 30 minutes, though some laboratory references suggest activity windows approaching two hours. The design intent is physiological mimicry: a GHRH-type signal that fires, elevates GH sharply, and then clears, leaving the pituitary's feedback mechanisms intact.

"A short peptide half-life is not a weakness, it is a design feature when the goal is preserving the pulsatile architecture of GH secretion."

For researchers using a Tesamorelin CJC1295 combination, appreciating these distinct pharmacokinetic profiles is essential before interpreting pulse data.


Comparing GH Pulse Amplitude and Secretion Patterns
Comparing GH Pulse Amplitude and Secretion Patterns

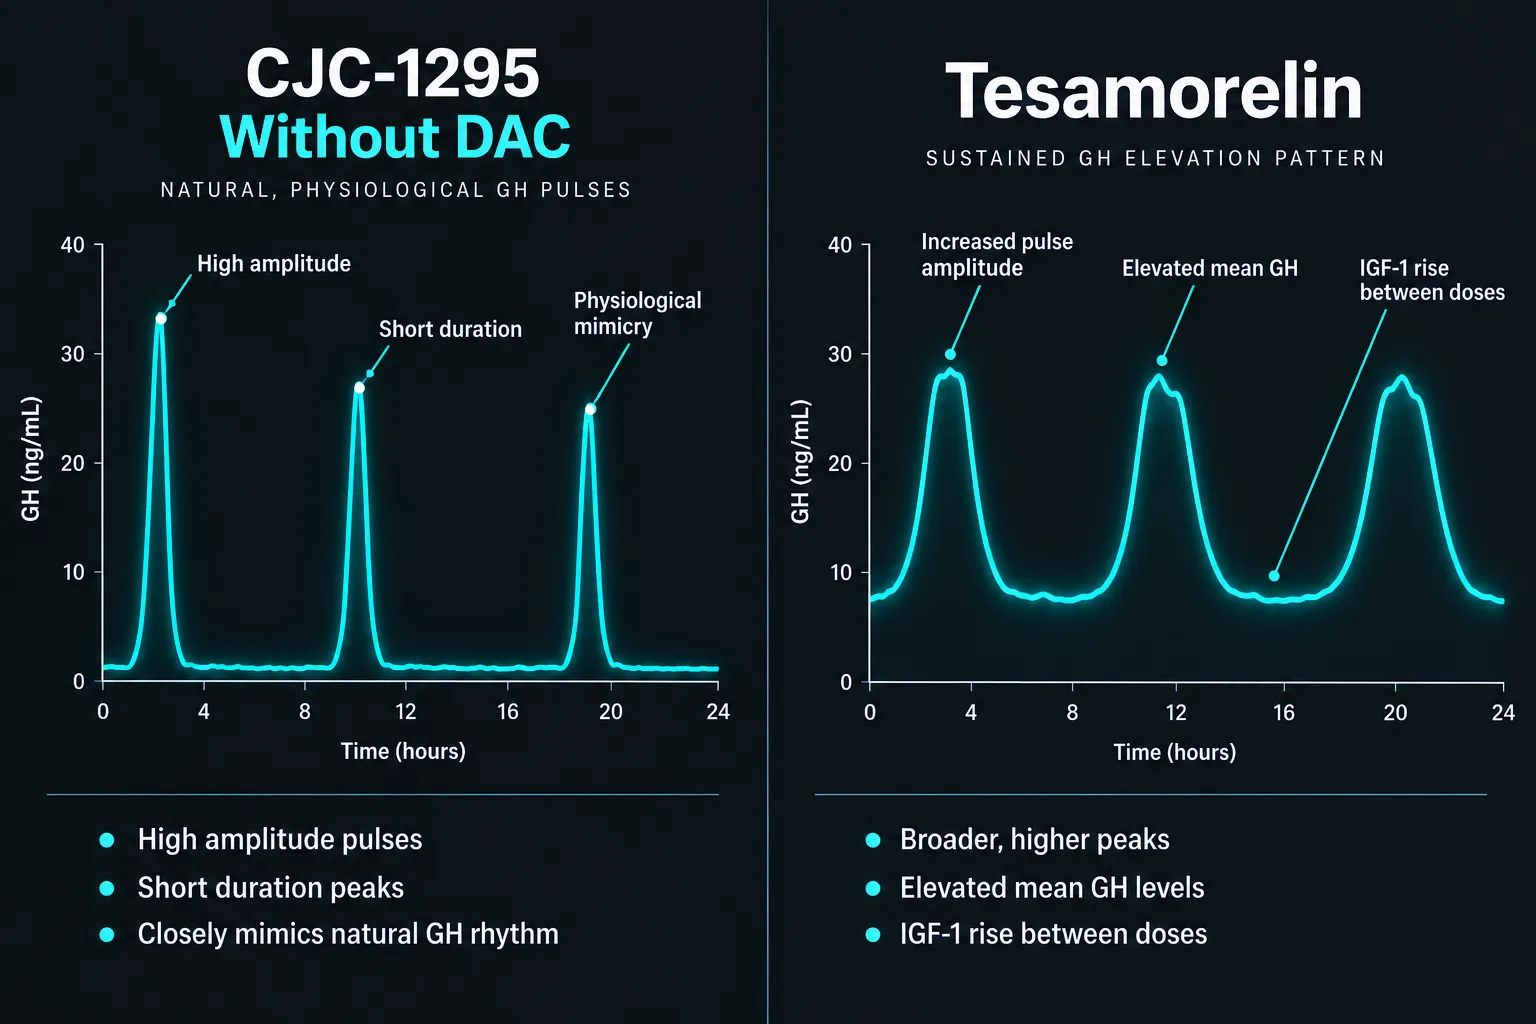
When examining CJC-1295 Without DAC vs. Tesamorelin: Pulsatile Growth Hormone Secretion Amplitude and Half-Life Metrics through the lens of pulse shape, three variables matter most: peak GH amplitude, pulse duration, and the number of pulses per unit time.

Tesamorelin's Effect on GH Pulsatility

Clinical pharmacology data for tesa show a consistent and well-characterized pattern:

  • Increased pulse amplitude, each GH burst reaches a higher peak concentration
  • Elevated mean GH across the 24-hour cycle
  • No significant change in pulse frequency, the pituitary does not fire more often, it fires harder
  • GH half-life preserved at approximately 13 to 16 minutes

This profile is valuable because it augments GH output while respecting the natural rhythm of secretion. Researchers tracking tesa dosage for fat loss protocols note that daily dosing keeps IGF-1 elevated between pulses, which is where much of the anabolic and lipolytic signaling occurs.

CJC-1295 Without DAC's Expected Pulse Profile

Direct human pharmacodynamic data for CJC-1295 Without DAC are limited compared to tesa's FDA-reviewed dataset. Based on available preclinical evidence and mechanistic reasoning:

  • Pulses are described as sharp and short-lived, with a steep rise and fall
  • The brief stimulation window is intended to produce a single clean GH spike per injection
  • Because albumin binding is absent, there is no prolonged receptor occupation that could blunt subsequent pulses
  • Frequent dosing (two to three times daily) or co-administration with a GH secretagogue is commonly used in research settings to optimize cumulative GH exposure

A popular research pairing involves adding ipamorelin to sharpen the amplitude further. Protocols and CJC1295 ipamorelin dosage guidance reflect this strategy of stacking a GHRH analog with a GH secretagogue for synergistic pulse control.

Metric Tesamorelin CJC-1295 Without DAC
Plasma half-life ~8-38 min ~30 min (up to ~2 hr)
GH pulse amplitude Significantly increased Sharp increase (short window)
Pulse frequency change Unchanged Unchanged (per injection)
IGF-1 elevation Sustained between doses Depends on dosing frequency
Human clinical data FDA-validated Limited / preclinical

Designing a Comparative Laboratory Protocol
Designing a Comparative Laboratory Protocol

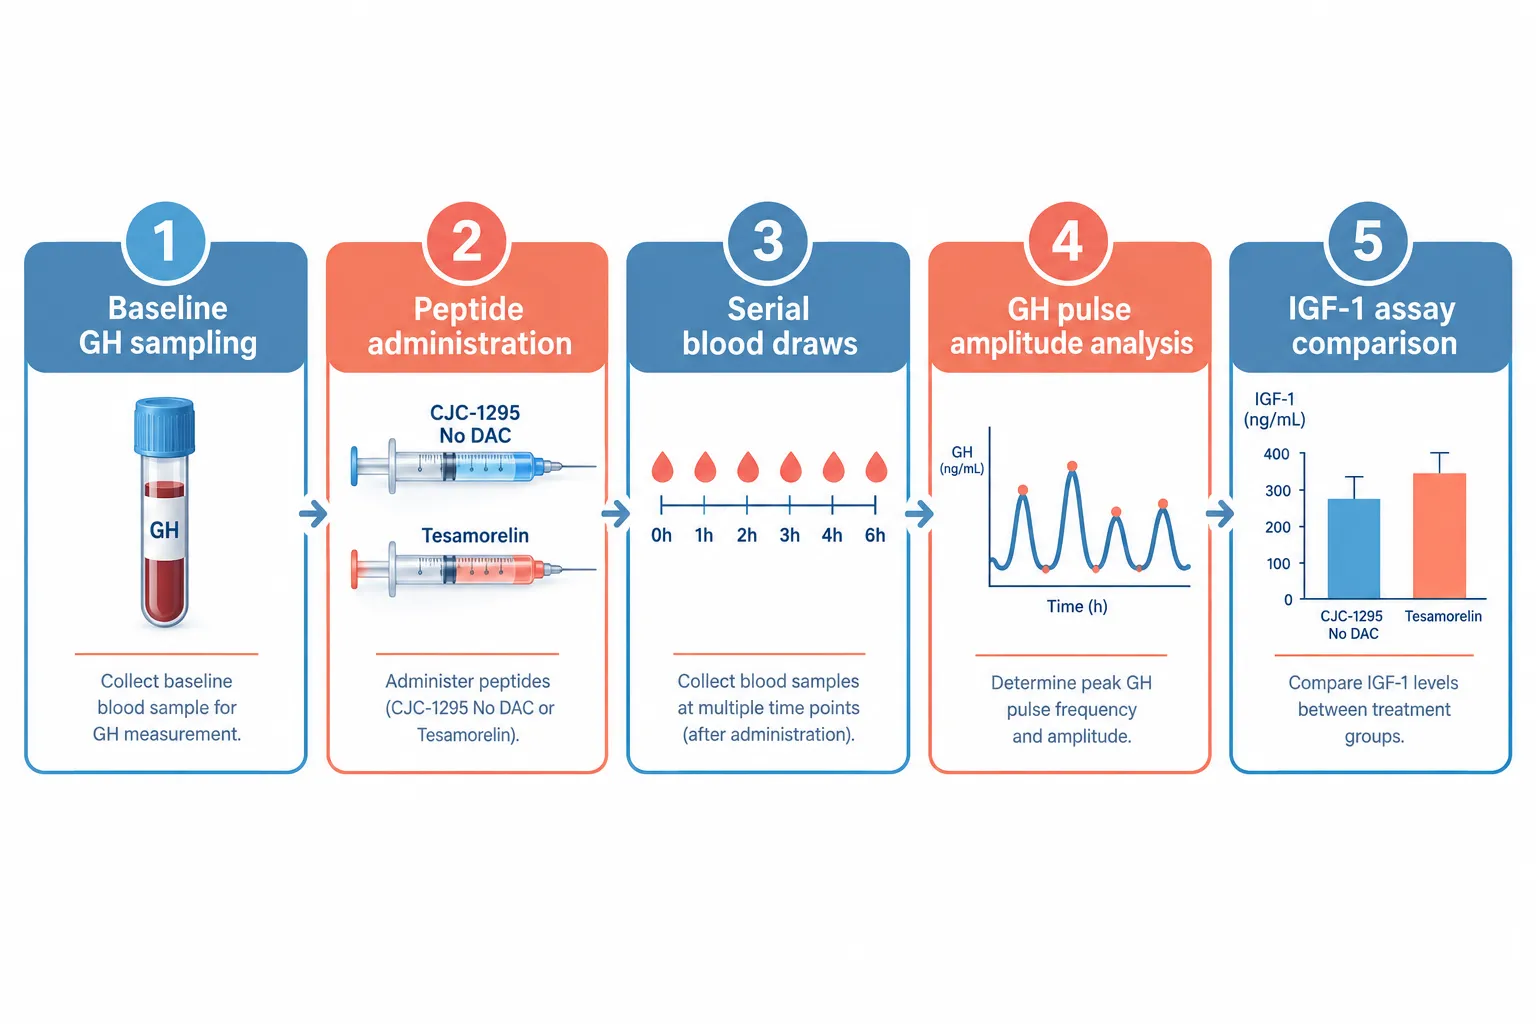
A methodologically sound side-by-side protocol measuring CJC-1295 Without DAC vs. Tesamorelin: Pulsatile Growth Hormone Secretion Amplitude and Half-Life Metrics in laboratory models would require several defined steps to generate interpretable data.

Step 1, Baseline sampling: Establish pre-intervention GH pulse frequency and amplitude using serial blood collection over a standardized window (typically 12 to 24 hours).

Step 2, Controlled peptide administration: Assign groups to equivalent molar doses of each peptide administered subcutaneously under identical conditions, controlling for time of day, fasting status, and co-administered agents.

Step 3, Serial GH measurement: Collect samples at 10- to 20-minute intervals post-injection to capture peak amplitude, pulse duration, and return-to-baseline timing.

Step 4, IGF-1 assay: Measure serum IGF-1 at defined intervals (e.g., 2, 6, 12, and 24 hours) to quantify downstream biological impact.

Step 5, Statistical deconvolution: Apply pulse detection algorithms to separate true GH pulses from baseline noise and calculate area under the curve (AUC) for each peptide condition.

This protocol framework is consistent with the approach used in published tesa pharmacodynamic work. Researchers interested in safety considerations before running combined protocols should review data on combining tesa with ipamorelin and consult available tesa side effects documentation.

For those working with multi-peptide formulations, resources on the Tesamorelin AOD9604 CJC1295 Ipamorelin 12mg blend provide context on how researchers combine these agents in practice.

Evidence Gaps That Limit Direct Comparison

The most important caveat in any 2026 analysis of this topic is straightforward: no published head-to-head clinical trial has directly compared CJC-1295 Without DAC and tesa on GH pulse amplitude under controlled conditions. Tesamorelin's data are robust and FDA-reviewed. CJC-1295 Without DAC data remain largely preclinical or mechanistically inferred. Any researcher drawing firm equivalency conclusions between the two peptides is extrapolating beyond the current evidence base.


Conclusion

The comparison of CJC-1295 Without DAC vs. Tesamorelin on pulsatile growth hormone secretion amplitude and half-life metrics reveals two peptides with overlapping mechanisms but meaningfully different pharmacokinetic profiles and evidence bases. Tesamorelin offers well-characterized pulse amplitude amplification with preserved pulsatile architecture, backed by clinical data. CJC-1295 Without DAC is designed for physiological GH pulse mimicry through its short clearance window, but lacks equivalent human trial data.

Actionable next steps for researchers:

  1. Use tesa's validated pharmacokinetic data as the methodological anchor when designing comparative GH pulse studies.
  2. Apply serial sampling protocols with defined collection intervals to capture true peak amplitude for CJC-1295 Without DAC.
  3. Include IGF-1 AUC as a secondary endpoint to reflect biological impact beyond plasma half-life.
  4. Consult current tesa dosage calculator tools and available blend dosing references before finalizing experimental parameters.
  5. Acknowledge the evidence gap explicitly in any published comparative analysis until direct head-to-head trial data become available.
https://www.puretestedpeptides.com/wp-content/uploads/2026/10/cjc-1295-without-dac-vs-tesamorelin-pulsatile-growth-hormone-secretion-amplitude.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-30 13:06:122026-10-30 13:06:12CJC-1295 Without DAC vs. Tesamorelin: Pulsatile Growth Hormone Secretion Amplitude and Half-Life Metrics

Tag Archive for: igf-1

Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols

Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols

July 24, 2026/0 Comments/by Pure Tested

Growth hormone secretion declines by roughly 14% per decade after age 30, a physiological reality that has driven sustained scientific interest in peptide-based GH secretagogues. Among the most studied pairing in preclinical and translational research is the Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols framework, which exploits two distinct receptor pathways to amplify pulsatile GH output in ways that neither compound achieves alone.

Isometric scientific illustration in bright daylight palette showing two distinct molecular pathway diagrams side by side —

Key Takeaways

  • Tesamorelin acts as a GHRH analog; ipamorelin acts as a ghrelin receptor agonist, together they engage complementary pathways.
  • Dual-pathway stimulation produces additive or potentially synergistic GH pulses compared to single-agent protocols.
  • Tesamorelin holds FDA-approved status for HIV-associated lipodystrophy; ipamorelin and the combination remain unapproved for any indication.
  • Dosing protocols in research settings are weight-independent, time-sensitive, and typically administered subcutaneously at night.
  • Researchers designing peptide stacks should treat this combination as an investigational model requiring rigorous experimental controls.

Individual Mechanisms: Two Pathways, One Goal

Understanding why the Ipamorelin and Tesamorelin Combination generates research interest begins with their separate mechanisms.

Tesamorelin is a stabilized analog of endogenous growth hormone-releasing hormone (GHRH). It binds GHRH receptors on somatotroph cells in the anterior pituitary, directly stimulating GH synthesis and secretion. Because it mirrors the body's own GHRH signal, the resulting GH pulse follows a physiologically normal pattern. Researchers studying tesa benefits note its well-characterized pharmacokinetic profile and the clinical data supporting its lipid-mobilization effects.

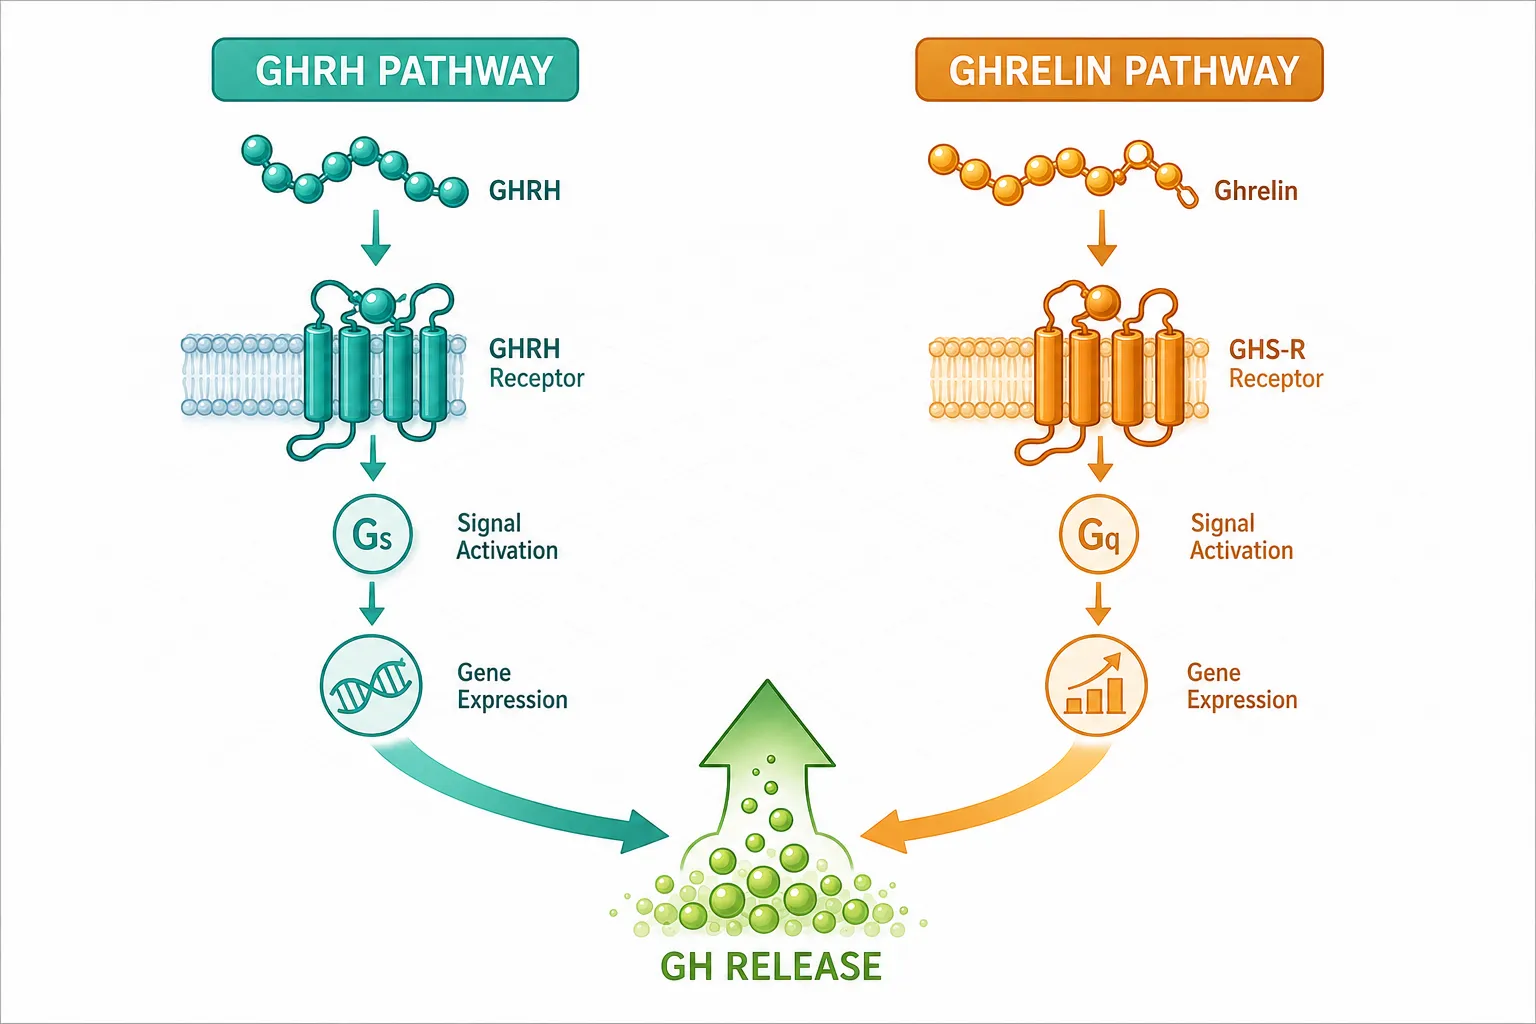
Ipamorelin belongs to a different class entirely. It is a selective ghrelin receptor (GHS-R1a) agonist, a pentapeptide that triggers GH release through the ghrelin pathway without meaningfully elevating cortisol or prolactin. This selectivity is a key research advantage. For a deeper look at how ipamorelin fits within broader GH secretagogue stacks, the CJC-1295 plus Ipamorelin research overview provides useful context.

"Two keys, two locks, one door", the GHRH pathway and the ghrelin pathway converge on the same somatotroph cell, and activating both simultaneously produces a GH pulse that exceeds what either key unlocks alone.

Why Dual-Pathway Activation Matters

The pituitary integrates signals from both GHRH and ghrelin receptors. When both are occupied concurrently:

  • Intracellular cAMP (via GHRH-R) and intracellular calcium (via GHS-R1a) rise together.
  • The two second-messenger cascades have a documented additive interaction at the somatotroph level.
  • The resulting GH pulse is larger and may be more sustained than single-receptor stimulation.

This is the mechanistic foundation for the synergistic GH secretagogue concept that makes the combination worth investigating.

Research Findings on the Ipamorelin and Tesamorelin Combination

Research Findings on the Ipamorelin and Tesamorelin Combination

Preclinical data consistently show that GHRH analogs and ghrelin-pathway agonists produce greater GH output when co-administered than when used separately. Tesamorelin's clinical track record, it is FDA-approved for reducing visceral adiposity in HIV-associated lipodystrophy, provides a validated pharmacological anchor. Ipamorelin's selectivity profile makes it a preferred ghrelin agonist in research designs that require minimal off-target hormonal noise.

Researchers comparing secretagogue classes should also review Tesamorelin vs. Sermorelin to understand how tesa's modified structure confers greater plasma stability than first-generation GHRH analogs.

Key observations from the literature on combined GH secretagogue protocols include:

Parameter Single GHRH Analog Single Ghrelin Agonist Combined Protocol
GH Pulse Amplitude Moderate Moderate Higher (additive/synergistic)
Cortisol Elevation Minimal Minimal Minimal
Prolactin Elevation Minimal Minimal Minimal
IGF-1 Upregulation Moderate Moderate Greater

Important regulatory note: Tesamorelin is FDA-approved only as monotherapy for a specific indication. Ipamorelin carries no regulatory approval. The combination is not approved by any regulatory authority and is appropriate only for controlled research settings.

For researchers exploring multi-peptide formulations, the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend represents a pre-formulated research option that adds a DAC-modified GHRH analog to the stack.

Dosing Protocols for Synergistic GH Secretagogue Research

Dosing Protocols for Synergistic GH Secretagogue Research

Designing a rigorous protocol around the Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols model requires attention to timing, dose selection, and experimental controls.

Timing Principles

GH is secreted in pulses, with the largest pulse occurring shortly after sleep onset. Research protocols typically align administration with this natural rhythm:

  • Preferred window: 30-60 minutes before sleep
  • Administration route: Subcutaneous injection (standard for both peptides)
  • Fasting state: A 2-hour fast before dosing reduces somatostatin tone and improves GH pulse amplitude

Commonly Referenced Research Doses

These figures appear in the preclinical and translational research literature and are provided for scientific reference only:

  • Tesamorelin: 1-2 mg per administration
  • Ipamorelin: 200-300 mcg per administration
  • Frequency: Once daily (evening) or twice daily (morning and evening) depending on study design

Researchers seeking dose-calculation guidance can consult the Tesamorelin dosage calculator for reference modeling.

Protocol Design Considerations

  • Cycling: Most research designs run 8-12 week active phases followed by 4-week washout periods to prevent receptor desensitization.
  • Controls: Include single-agent arms (tesa alone, ipamorelin alone) to quantify the additive contribution.
  • Biomarkers: Track serum IGF-1, fasting GH pulse amplitude, and body composition metrics as primary endpoints.
  • Safety monitoring: Assess fasting glucose and insulin sensitivity at baseline and at 4-week intervals given GH's known effects on glucose metabolism.

For researchers interested in how this combination compares within broader secretagogue stacks, the Sermorelin, Ipamorelin, and CJC-1295 combination overview offers comparative mechanistic context. Additionally, the safety considerations for combining Tesamorelin with CJC and Ipamorelin addresses common protocol safety questions.

Conclusion

The Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols framework offers a mechanistically coherent strategy for amplifying pulsatile GH secretion in research models. By simultaneously engaging the GHRH receptor pathway through tesa and the ghrelin receptor pathway through ipamorelin, researchers can generate GH pulses that exceed single-agent outputs while maintaining a favorable hormonal selectivity profile.

Actionable next steps for researchers:

  1. Review the regulatory landscape, tesa's FDA-approved monotherapy status sets a pharmacological benchmark; the combination remains strictly investigational.
  2. Design protocols with single-agent control arms to isolate the synergistic contribution.
  3. Align dosing with natural GH pulse timing (evening administration, fasted state).
  4. Monitor IGF-1, glucose metabolism, and body composition as primary experimental endpoints.
  5. Plan 8-12 week active cycles with structured washout periods to preserve receptor sensitivity.

Rigorous experimental design, not anecdotal stacking, is what transforms a mechanistically promising combination into reproducible, publishable science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/ipamorelin-and-tesamorelin-combination-synergistic-gh-secretagogue-research-and.webp 672 1008 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-24 13:09:592026-11-13 20:06:28Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research

CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research

June 28, 2026/0 Comments/by Pure Tested

A peptide with a 30-minute half-life may sound like a limitation. In growth hormone research, it is often the point. CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research is a question that cuts to the core of how researchers design protocols that respect the body's natural hormonal rhythms rather than override them.

Also known as Modified GRF 1-29, CJC-1295 without DAC is a synthetic analog of growth hormone-releasing hormone (GHRH). Its short active window is not a flaw in the design — it is the design.

Key Takeaways

  • CJC-1295 without DAC has a half-life of approximately 30 minutes, supporting pulsatile GH release
  • The absence of the Drug Affinity Complex (DAC) distinguishes it from the longer-acting DAC variant
  • Pulsatile GH secretion more closely mirrors natural physiology and may reduce receptor desensitization
  • It is frequently paired with ipamorelin to target complementary GH-release pathways
  • CJC-1295 without DAC is not FDA-approved and is intended strictly for research purposes

Key Takeaways

Understanding the Half-Life Difference in CJC-1295 Without DAC Research

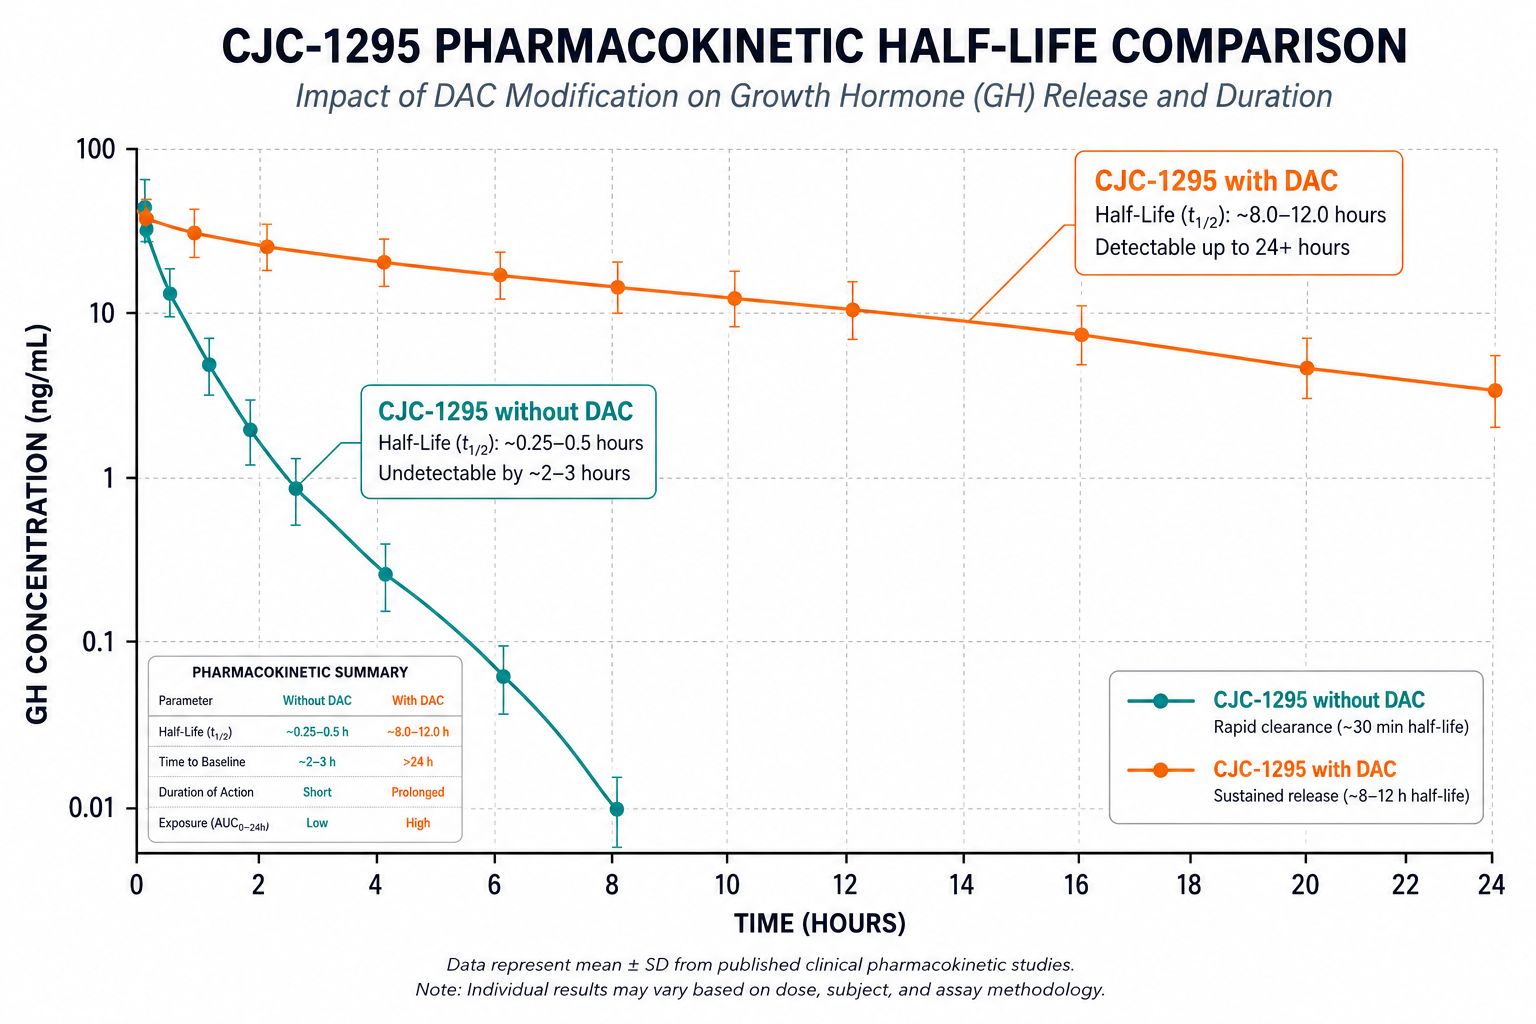
Half-life determines how long a compound remains active in a biological system. For CJC-1295 without DAC, that window is roughly 30 minutes. For the DAC version, the half-life stretches to approximately 5.8 to 8.1 days.

That difference is not trivial. It changes everything about how GH is released.

Variant Half-Life GH Release Pattern
CJC-1295 without DAC ~30 minutes Pulsatile, physiological
CJC-1295 with DAC ~5.8–8.1 days Sustained, continuous

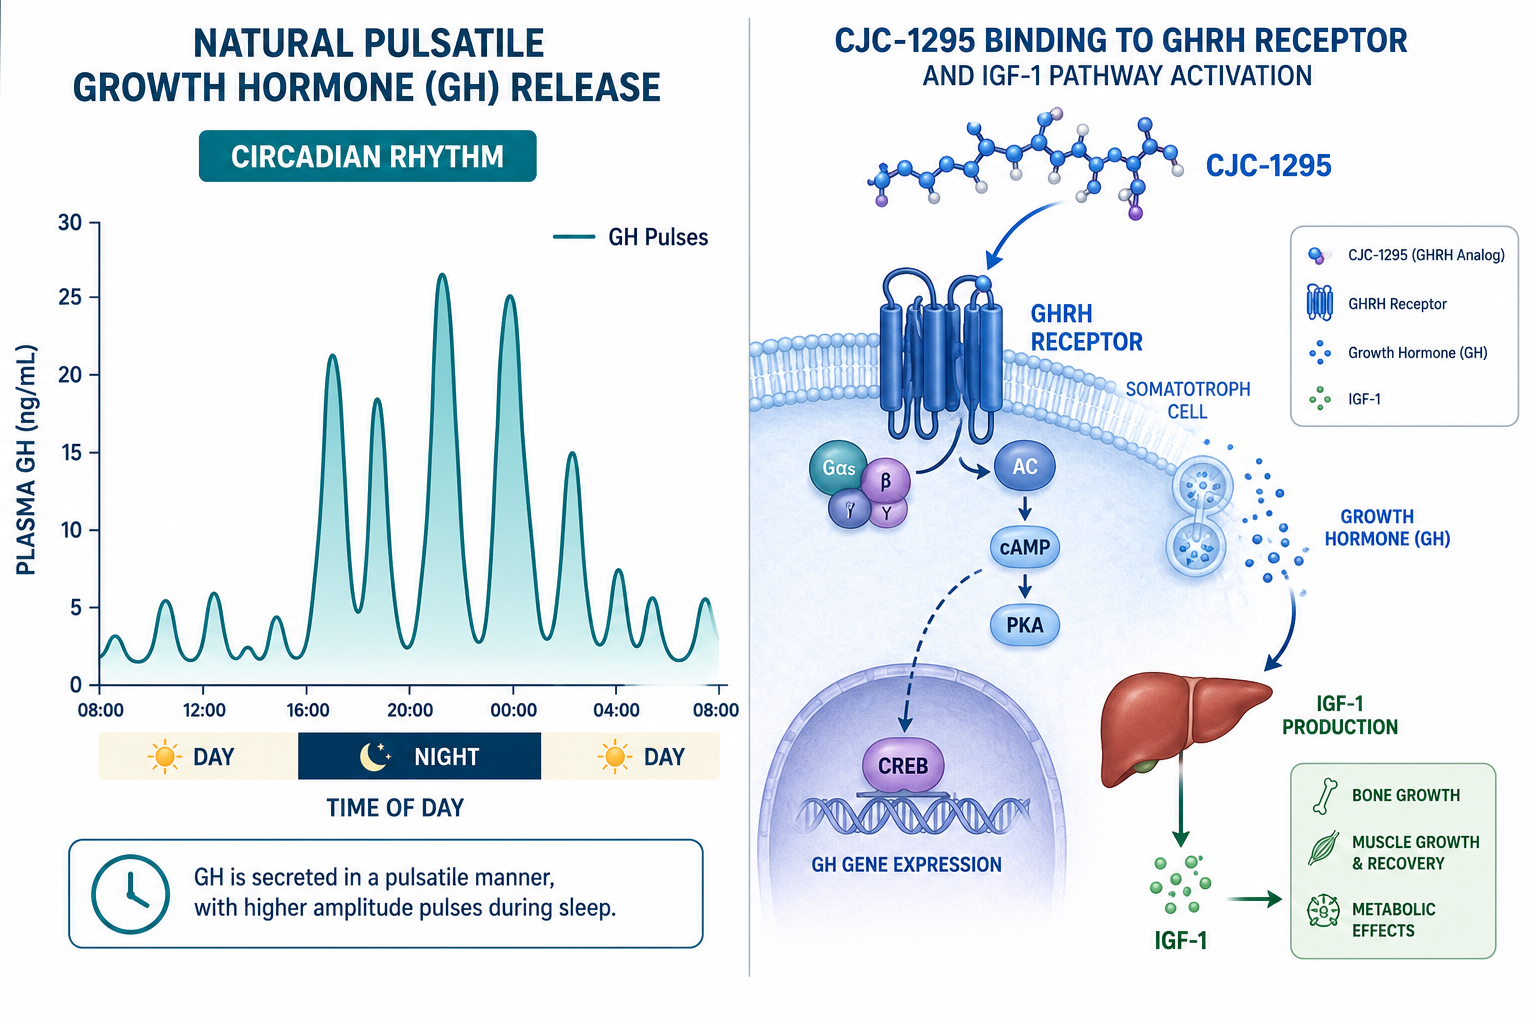
The body does not release GH in a steady stream. It releases it in pulses — sharp peaks followed by quiet troughs. This rhythm is tied to sleep cycles, metabolic signaling, and feedback loops involving IGF-1. A compound that mimics this pattern is considered more physiologically aligned than one that maintains constant elevation.

"The short half-life of the no-DAC variant allows researchers to time GH pulses with precision, which is central to protocols designed around natural secretion windows."

For a deeper look at how the DAC modification changes the pharmacological profile, the CJC-1295 with DAC deeper dive offers a useful comparison.


Mechanism of Action: How the No-DAC Version Triggers GH Pulses

CJC-1295 without DAC binds to GHRH receptors on pituitary somatotroph cells. This binding stimulates the release of GH, which in turn drives IGF-1 production in the liver. The cascade is well-characterized in the scientific literature.

What makes the no-DAC version distinct is its rapid clearance. Because it leaves the system quickly, GH levels rise sharply and then return to baseline — closely matching the body's endogenous pattern.

Why this matters in research:

  • Avoids prolonged receptor activation that can lead to desensitization
  • Allows multiple dosing windows within a single day
  • Enables researchers to observe GH pulse responses in controlled intervals

Typical research protocols use doses of 100–300 mcg administered two to three times daily, often timed around sleep onset and morning windows when natural GH secretion is highest. Cycles in research settings commonly run 12 to 16 weeks.

The CJC-1295 product page provides additional catalog context for researchers sourcing this compound.


Mechanism of Action: How the No-DAC Version Triggers GH Pulses

CJC-1295 Without DAC and Ipamorelin: A Common Research Pairing

One of the most studied combinations in GH research pairs CJC-1295 without DAC with ipamorelin. These two compounds work through different but complementary pathways.

  • CJC-1295 without DAC activates the GHRH receptor, amplifying the GH pulse
  • Ipamorelin activates the growth hormone secretagogue receptor (GHSR), independently triggering GH release

Together, they produce a stronger, more synchronized GH response than either compound alone. Researchers value this pairing because it targets two separate mechanisms while still producing a pulsatile, time-limited GH spike.

Pre-formulated blends are available for research use, including the CJC-1295 and ipamorelin combination and the CJC-1295 plus IPA research blend.

For researchers exploring broader GH-axis protocols, the tesa vs ipamorelin comparison provides useful context on how different GHRH analogs differ in their pharmacological profiles.


CJC-1295 Without DAC and Ipamorelin: A Common Research Pairing

Storage, Safety, and Research Considerations

Lyophilized CJC-1295 without DAC should be stored at 2–8°C. Once reconstituted, it remains stable under refrigeration for up to 30 days.

The available safety data — drawn from studies on the parent CJC-1295 compound — suggest reasonable tolerability at research doses, with no serious adverse reactions reported at doses of 30 or 60 mcg/kg. However, long-term safety data remain limited, and the compound is not FDA-approved for human or veterinary use.

The evidence base includes 18 human studies, 126 animal studies, and over 56 published reviews — a substantial foundation, though researchers should note that studies specific to the no-DAC variant are less numerous than those on the DAC form.

Researchers interested in broader peptide research contexts may also find value in reviewing BPC-157 research documentation and TB-500 and BPC-157 regeneration research as complementary areas of study.


Conclusion

CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research comes down to one core principle: shorter is sometimes smarter. A 30-minute half-life is not a compromise — it is a tool that allows researchers to replicate pulsatile GH dynamics with precision.

Actionable next steps for researchers in 2026:

  1. Review the pharmacokinetic literature on Modified GRF 1-29 before designing protocols
  2. Consider the ipamorelin pairing to target complementary GH-release pathways
  3. Source compounds from verified suppliers with documented purity testing
  4. Align dosing windows with natural GH secretion peaks (sleep onset, morning)
  5. Monitor IGF-1 markers as a downstream indicator of GH pulse activity

Understanding half-life is not a detail — it is the foundation of responsible, reproducible growth hormone research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/CJC-1295-Without-DAC-Why-Half-Life-Matters-in-Growth-Hormone-Research.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-28 13:04:042026-11-22 02:18:01CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research
CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design

CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design

June 21, 2026/0 Comments/by Pure Tested

A single structural modification — the addition of a Drug Affinity Complex linker — transforms a short-acting peptide into one with a half-life measured in days rather than minutes. That pharmacokinetic gap sits at the heart of the debate around CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design, and it shapes every variable a researcher must account for when designing a growth hormone (GH) study.

Key Takeaways

  • CJC-1295 with DAC binds covalently to serum albumin, extending its half-life to approximately 6-8 days.
  • CJC-1295 without DAC (Mod GRF 1-29) has a half-life of roughly 30 minutes and produces pulsatile GH release.
  • The DAC variant sustains GH elevation but may disrupt natural pulsatile secretion and risk receptor desensitization.
  • Experimental design choices — dosing frequency, combination partners, and outcome measures — differ significantly between the two forms.
  • Researchers often pair CJC-1295 without DAC with GHRPs like Ipamorelin to closely mimic physiological GH rhythms.

Key Takeaways

The Molecular Difference: What DAC Actually Does

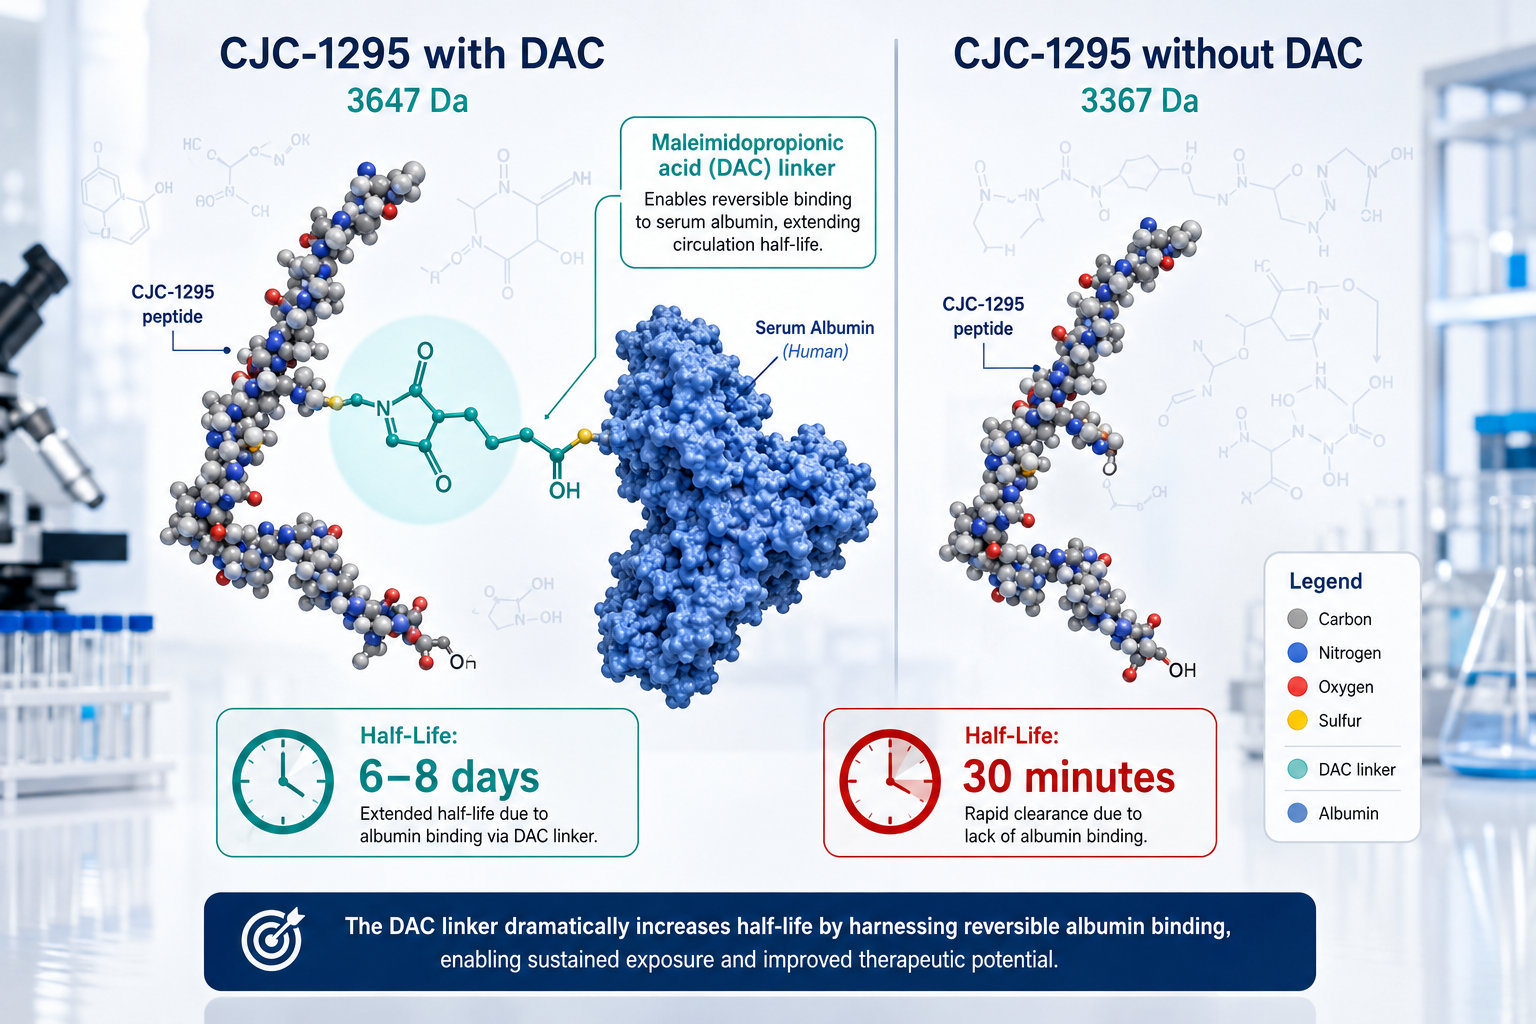
The Drug Affinity Complex (DAC) is a maleimidopropionic acid linker attached to the C-terminus of CJC-1295. This addition allows the peptide to form a covalent bond with the Cys34 residue of serum albumin, effectively anchoring it to a long-lived carrier protein circulating in the bloodstream.

The result is a meaningful increase in molecular weight — from approximately 3,367 Da (without DAC) to roughly 3,647 Da (with DAC) — and a dramatic extension of circulating half-life.

Feature CJC-1295 with DAC CJC-1295 without DAC
Half-life ~6-8 days ~30 minutes
Molecular weight ~3,647 Da ~3,367 Da
Albumin binding Covalent (Cys34) None
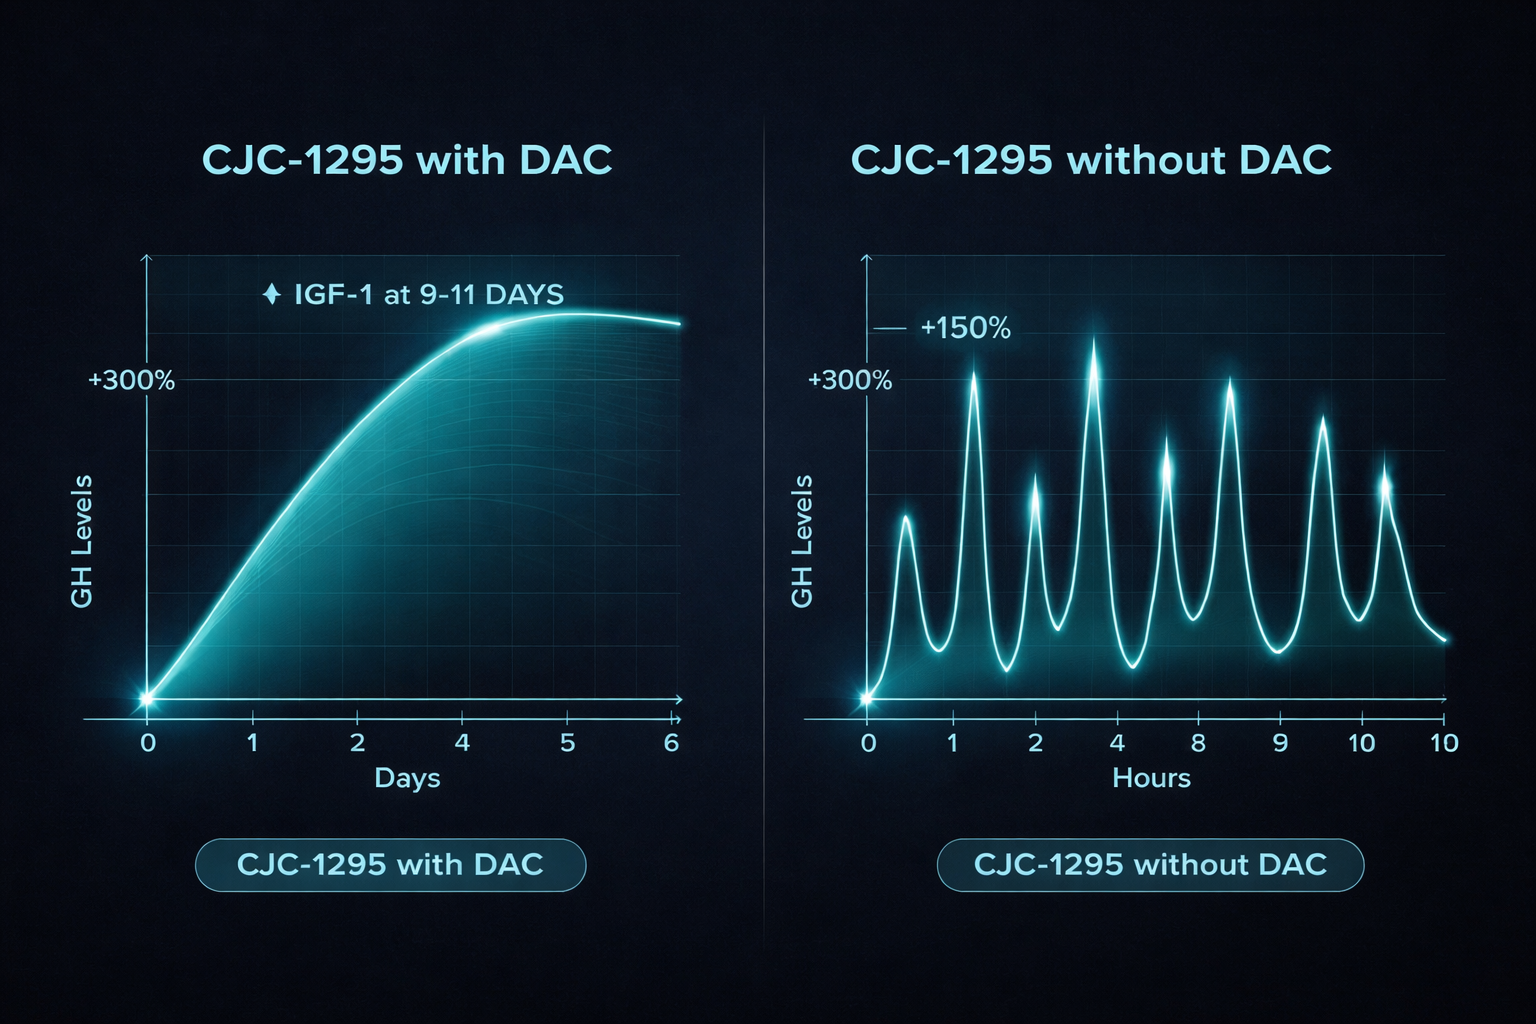
GH release pattern Sustained, continuous Pulsatile, transient
Dosing frequency Once or twice weekly Multiple times daily

For researchers exploring CJC-1295 research findings, understanding this structural distinction is the essential first step before any protocol is designed.


GH Secretion Patterns: Sustained Elevation vs. Physiological Pulses

GH Secretion Patterns: Sustained Elevation vs. Physiological Pulses

The pharmacokinetic difference between the two variants produces fundamentally different growth hormone secretion profiles, each with distinct research implications.

CJC-1295 with DAC: Continuous Stimulation

Clinical data from Phase I and II trials conducted in the mid-2000s showed that a single dose of CJC-1295 with DAC produced a 2-10 fold increase in GH levels lasting up to six days. IGF-1 levels remained elevated for 9-11 days following that single administration. This sustained profile makes the DAC variant well-suited for studies requiring prolonged GH elevation without frequent dosing.

However, continuous GH stimulation carries a notable concern: receptor desensitization. Prolonged activation of GHRH receptors may reduce their sensitivity over time, potentially blunting the GH response in longer-term protocols.

CJC-1295 without DAC: Mimicking Natural Rhythms

CJC-1295 without DAC — also called Mod GRF 1-29 — produces short, sharp GH pulses that closely mirror the body's natural pulsatile secretion pattern. This pulsatility is considered important for maintaining insulin sensitivity and preserving receptor responsiveness.

"Pulsatile GH release is not merely a physiological quirk — it is a functional requirement for downstream signaling fidelity."

Researchers focused on physiological accuracy tend to favor the non-DAC variant. It is frequently combined with growth hormone-releasing peptides (GHRPs) such as Ipamorelin to amplify pulsatile release. The Sermorelin, Ipamorelin, and CJC-1295 combination represents a common multi-peptide research approach built on this principle. Similarly, Ipamorelin and Sermorelin stack research provides additional context for synergistic GHRH-GHRP protocols.


Experimental Design Considerations for Each Variant

Experimental Design Considerations for Each Variant

Choosing between these two forms in a research context is not simply a matter of convenience — it determines the biological question the experiment can validly answer.

When to Use the DAC Variant

  • Studies examining sustained GH elevation and downstream IGF-1 responses
  • Protocols where infrequent dosing (once or twice weekly) is operationally necessary
  • Research into conditions historically linked to GH deficiency, reflecting the peptide's Phase II trial history

When to Use the Non-DAC Variant

  • Protocols designed to replicate natural pulsatile GH secretion
  • Studies assessing receptor sensitivity over time
  • Combination research with GHRPs, where timing and pulse synchronization matter

For researchers also exploring related GHRH analogs, comparing Tesamorelin vs. Sermorelin offers useful pharmacokinetic context. The Tesamorelin and CJC-1295 blend research further illustrates how multi-peptide designs can address complex GH axis questions. Researchers interested in body composition outcomes may also find the Tesamorelin body composition research themes page a valuable reference point.

Dosing frequency is perhaps the most practical design variable. The DAC variant's weekly schedule reduces protocol complexity, while the non-DAC variant's multiple-daily-injection requirement demands tighter experimental control but yields data more reflective of physiological GH dynamics.


Conclusion

The comparison of CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design ultimately comes down to one core question: does the research require sustained GH elevation or physiological pulsatility?

The DAC variant offers convenience and prolonged action through albumin binding, making it appropriate for sustained-elevation protocols. The non-DAC variant preserves natural GH rhythm, reduces receptor desensitization risk, and pairs effectively with GHRPs for synergistic research designs.

Actionable next steps for researchers in 2026:

  1. Define the GH secretion profile your study requires before selecting a variant.
  2. Account for dosing frequency in your experimental timeline and resource planning.
  3. Consider combination protocols with verified GHRPs when pulsatile secretion fidelity is the priority.
  4. Review available CJC-1295 research findings and related blend data to inform protocol selection.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/CJC-1295-with-DAC-vs.-Without-DAC-Impact-on-Growth-Hormone-Secretion-and-Experimental-Design.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-21 13:07:122026-11-22 02:17:57CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design
Tesamorelin and Ipamorelin: How the Two Growth Hormone Secretagogues Differ Mechanistically

Tesamorelin and Ipamorelin: How the Two Growth Hormone Secretagogues Differ Mechanistically

June 15, 2026/0 Comments/by Pure Tested

Two peptides. Two completely different locks on the same door. Tesamorelin and Ipamorelin are both classified as growth hormone secretagogues, yet they reach the pituitary gland by separate molecular routes, produce distinct GH secretion patterns, and serve different research purposes. Understanding exactly how these two growth hormone secretagogues differ mechanistically is not just academic — it shapes how researchers design protocols and interpret outcomes.

Key Takeaways

  • Tesamorelin is a GHRH analog that binds the GHRH receptor; ipamorelin is a ghrelin mimetic that binds the GHS-R1a receptor — two entirely separate receptor systems.
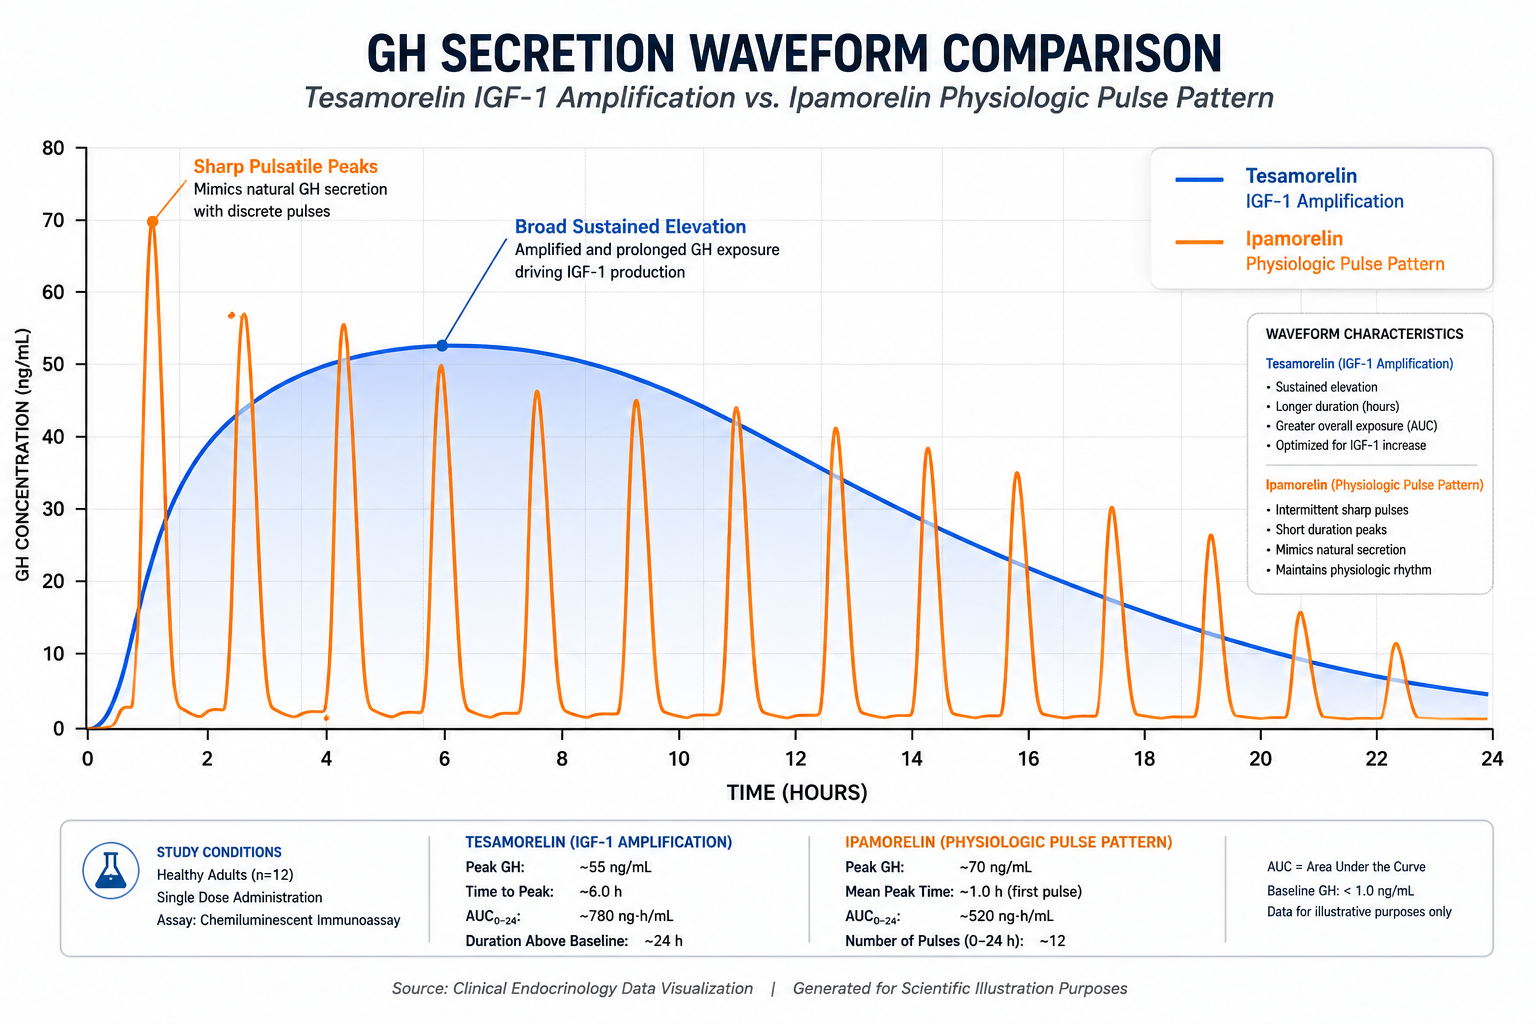
  • Tesamorelin drives a sustained elevation in GH and IGF-1; ipamorelin generates short, pulsatile GH spikes that mirror natural secretory rhythms.
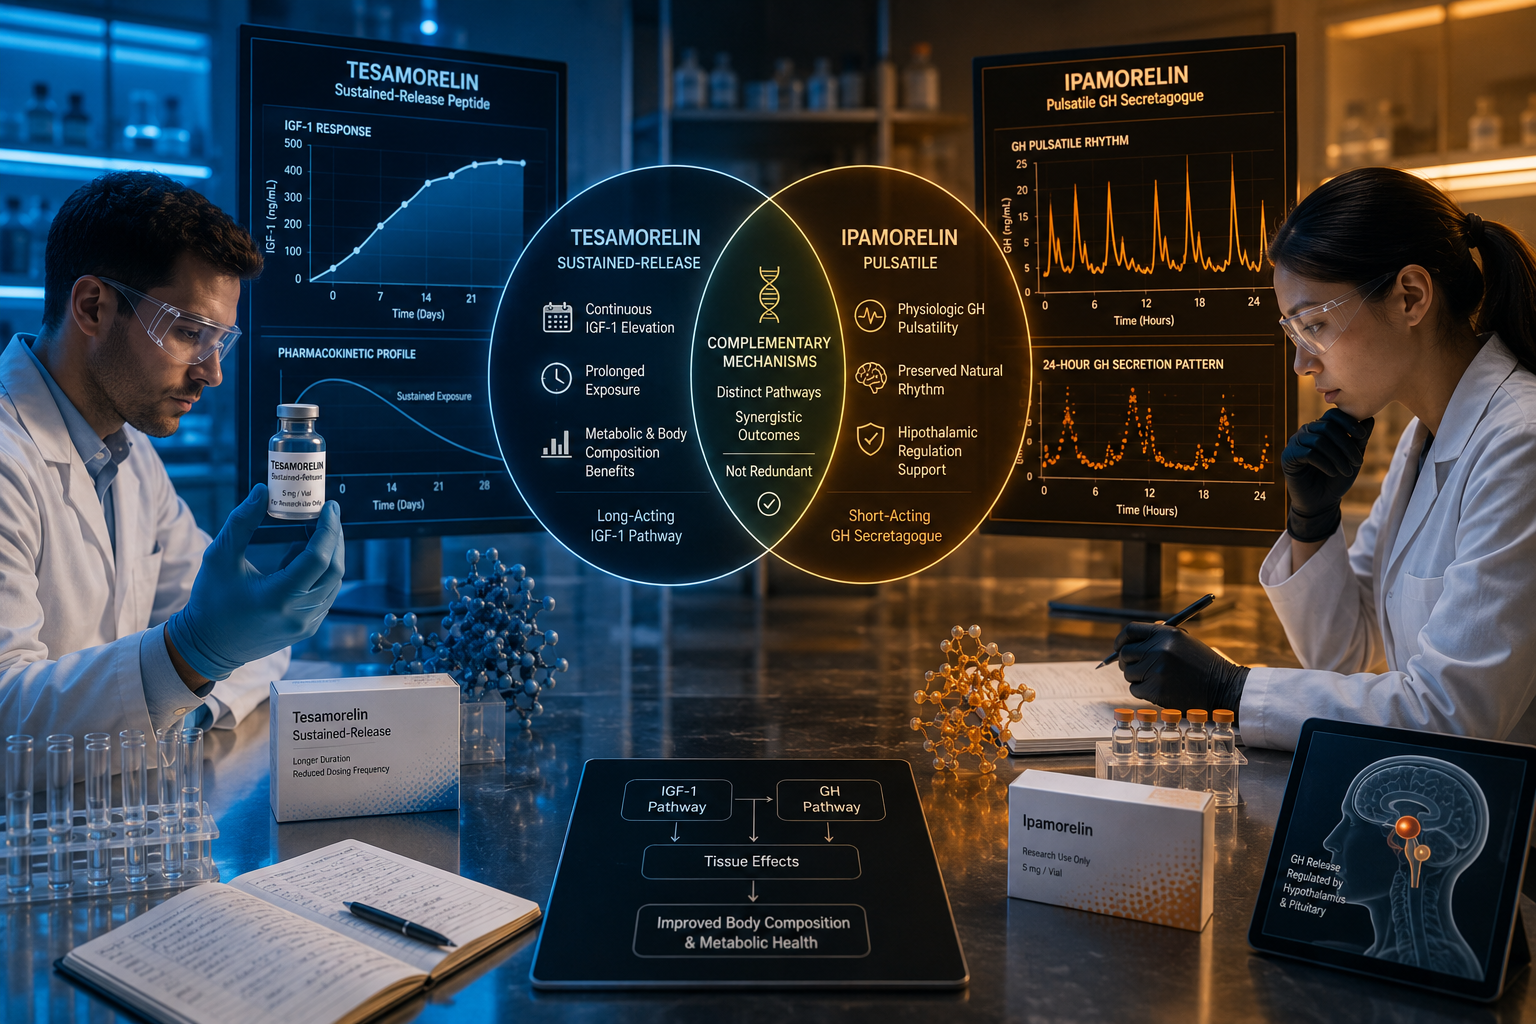
  • Because they target different upstream nodes of the GH axis, the two peptides are complementary rather than redundant.
  • Ipamorelin is noted for high selectivity — it stimulates GH release with minimal effect on cortisol or prolactin.
  • Researchers studying the GH axis benefit from understanding both pathways before designing combination or standalone protocols.

Receptor-Level Differences: Where the Pathways Diverge

Receptor-Level Differences: Where the Pathways Diverge

The clearest way to understand Tesamorelin and Ipamorelin and how the two growth hormone secretagogues differ mechanistically is to start at the receptor.

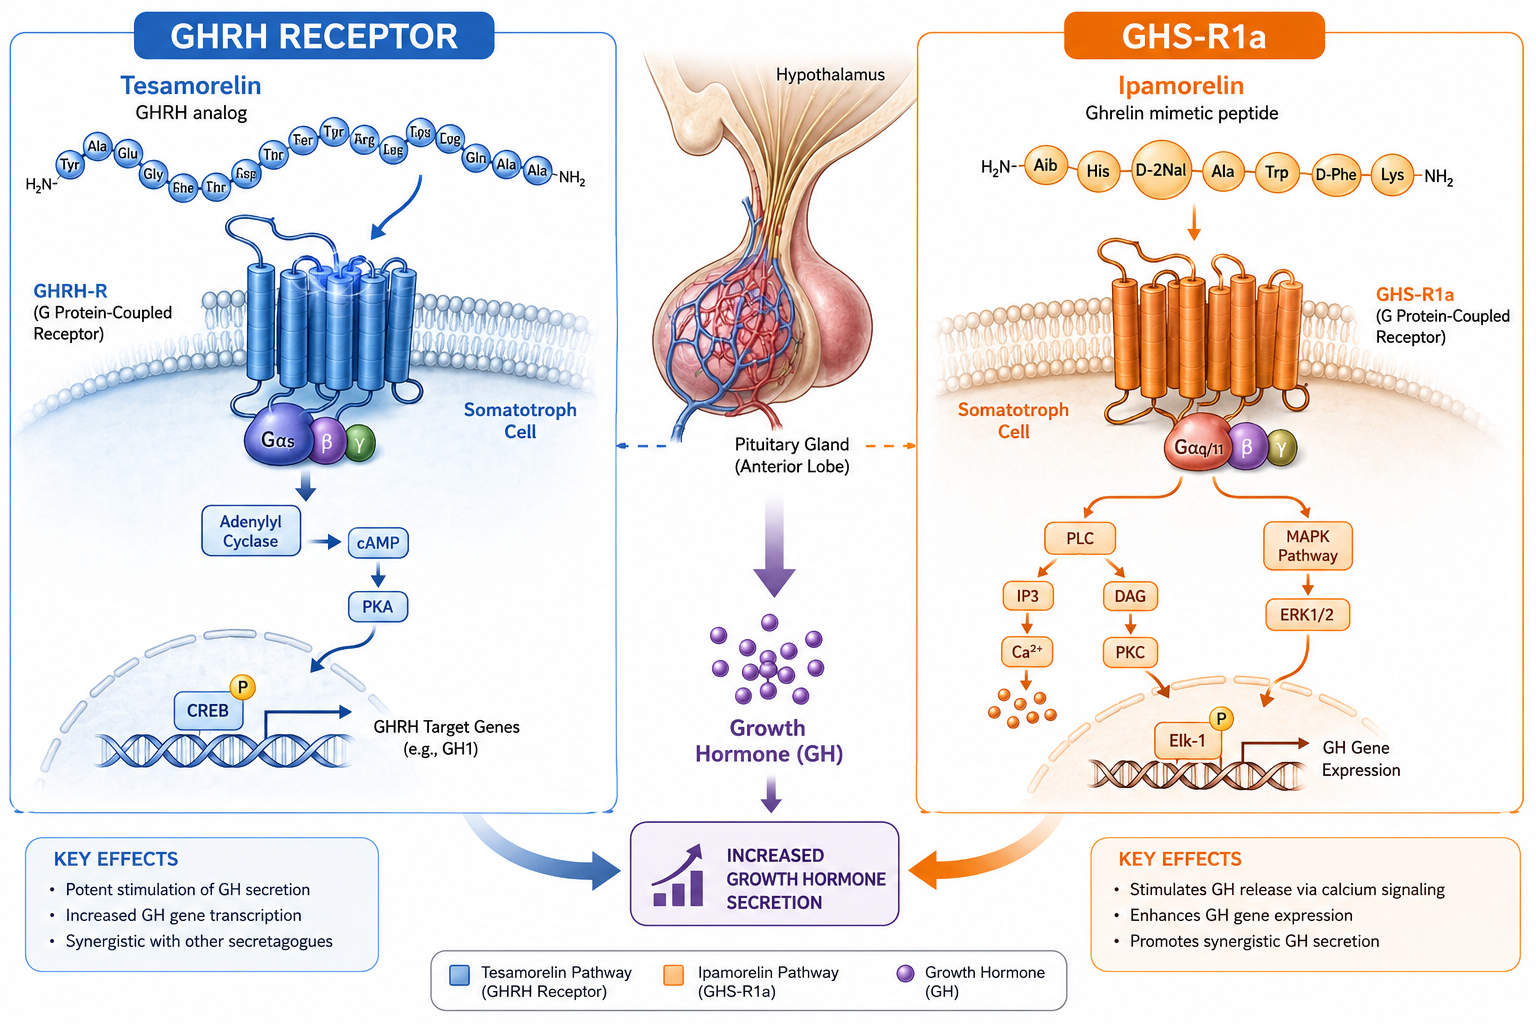
Tesamorelin is a synthetic analog of endogenous growth hormone-releasing hormone (GHRH). It binds selectively to the GHRH receptor located on pituitary somatotroph cells. By occupying this receptor, tesa amplifies the hypothalamic GHRH signal, prompting somatotrophs to produce and release more growth hormone. Its structure closely mirrors native GHRH(1-44) but includes a trans-3-hexenoic acid modification that extends its stability in plasma — a key reason it outperforms unmodified GHRH in sustained signaling.

Ipamorelin, by contrast, is a selective agonist of the ghrelin receptor, formally called the Growth Hormone Secretagogue Receptor type 1a (GHS-R1a). This receptor is pharmacologically and structurally distinct from the GHRH receptor. Ipamorelin acts as a ghrelin mimetic, meaning it mimics the hunger-signaling peptide ghrelin to unlock GH release through a pathway that operates independently of GHRH. Crucially, ipamorelin achieves this with high receptor selectivity — it does not significantly activate pathways that elevate cortisol or prolactin, which distinguishes it from older, less selective GHS compounds.

Feature Tesamorelin Ipamorelin
Receptor target GHRH receptor GHS-R1a (ghrelin receptor)
Peptide class GHRH analog Ghrelin mimetic
Signaling pathway GHRH axis Ghrelin axis
Cortisol/prolactin effect Minimal Minimal

For a deeper look at tesa's pharmacology, the science behind tesa provides useful foundational context.


GH Secretion Patterns: Sustained Amplification vs Pulsatile Spikes

GH Secretion Patterns: Sustained Amplification vs Pulsatile Spikes

Receptor differences translate directly into different hormonal output profiles — and this is where the practical research implications become most visible.

Tesamorelin produces a more sustained elevation in both GH and insulin-like growth factor 1 (IGF-1). Because it continuously reinforces the GHRH signal, circulating IGF-1 rises measurably over time. Clinical data show this sustained IGF-1 increase drives downstream metabolic effects, particularly visceral fat reduction in HIV-associated lipodystrophy — the only FDA-approved indication for tesamorelin. Researchers often position tesa as the "heavy-lift" GH/IGF-1 amplifier within the GH axis. For those tracking outcomes over time, the tesa before and after data illustrates how this sustained signaling manifests in measurable endpoints.

Ipamorelin generates short-lived, pulsatile GH peaks. These bursts closely mimic the natural GH secretory rhythm the body uses throughout the day and during sleep. Rather than chronically flattening or overriding the pulsatile rhythm, ipamorelin reinforces it. This makes ipamorelin a "pulse-shaping" secretagogue — one that works with the body's existing GH architecture rather than overwriting it.

"Tesamorelin amplifies the signal; ipamorelin restores the rhythm."

This distinction matters for researchers concerned about receptor desensitization or downstream feedback suppression. Sustained GHRH receptor stimulation carries a different long-term receptor dynamics profile than intermittent GHS-R1a activation.

Researchers interested in ipamorelin's standalone profile can explore whether ipamorelin is the most beneficial peptide for a broader discussion of its research applications.


Research Implications: Pairing, Separating, and Protocol Design

Research Implications: Pairing, Separating, and Protocol Design

Understanding Tesamorelin and Ipamorelin and how the two growth hormone secretagogues differ mechanistically has direct implications for protocol design.

Because the two peptides act on separate receptor systems, they are not redundant — they target different upstream control nodes of the GH axis. This is why combination approaches appear in the research literature. When used together, tesa provides sustained IGF-1 elevation through the GHRH pathway while ipamorelin adds pulsatile GH bursts through the ghrelin pathway. The result is a more complete stimulation of GH secretion than either agent alone can produce. Researchers considering this approach can review safety considerations for combining tesa with ipamorelin before designing protocols.

For researchers who prefer standalone use, the choice depends on the research question:

  • Choose tesa when the goal is sustained IGF-1 elevation and metabolic endpoints. See tesa dosage guidance for reference ranges used in research settings.
  • Choose ipamorelin when the goal is pulsatile GH reinforcement with minimal hormonal side effects. The ipamorelin research overview covers its selectivity profile in detail.

Researchers comparing tesa to other GHRH analogs may also find the tesa vs sermorelin comparison useful for situating tesa within the broader GHRH analog class.

One additional consideration: peptide purity directly affects receptor binding fidelity. Impure peptides produce inconsistent receptor activation, making mechanistic conclusions unreliable. Sourcing from suppliers with verified quality testing protocols is a non-negotiable step for credible research.


Conclusion

Tesamorelin and ipamorelin are not interchangeable tools — they are complementary instruments that operate on separate molecular circuits within the GH axis. Tesamorelin amplifies GH and IGF-1 through sustained GHRH receptor engagement; ipamorelin restores physiologic GH pulsatility through selective GHS-R1a activation. Researchers who understand this mechanistic split can design more precise protocols, interpret results more accurately, and avoid the common mistake of treating all growth hormone secretagogues as functionally equivalent.

Actionable next steps for researchers:

  • Map the specific GH axis endpoint under study before selecting a peptide.
  • Review the receptor selectivity and hormonal side-effect profiles of each compound.
  • If combining both agents, study the complementary pathway rationale and available safety data.
  • Verify peptide purity through third-party testing before any research use.
  • Consult dosage reference data and existing clinical literature to anchor protocol design.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Tesamorelin-and-Ipamorelin-How-the-Two-Growth-Hormone-Secretagogues-Differ-Mechanistically.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-15 13:03:312026-11-22 02:17:50Tesamorelin and Ipamorelin: How the Two Growth Hormone Secretagogues Differ Mechanistically
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout
  • About
  • Contact
  • COA / Lab Testing
  • Shipping Policy
  • Terms and Conditions
  • Research Use Disclaimer

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top