Trazodone and Peptide Appetite Studies: Separating Sedation, Sleep, Food Intake, and Metabolic Signaling
{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Trazodone and Peptide Appetite Studies' in crisp white sans-serif on a deep semi-transparent navy overlay panel, centered with 8% safe margins from every edge. Background: editorial close-up of a scientific laboratory bench featuring a molecular structure model, peptide vials, and a sleep EEG readout printout side by side under cool white studio lighting. Teal and navy color palette. Magazine cover aesthetic, editorial quality, no price tables, no checkmarks.","content":["Annotated mechanism-of-action diagram, landscape format (1536×1024), illustrating the pharmacological separation between trazodone sedation and appetite peptide signaling. Four labeled zones arranged left to right: Zone 1 labeled 'H1 Receptor Blockade / Sedation', Zone 2 labeled 'Serotonin Reuptake Inhibition', Zone 3 labeled 'Sleep Architecture Shift', Zone 4 labeled 'Indirect Ghrelin / Leptin Effect'. Callout lines point from each zone to a central trazodone molecule illustration. Teal, white, and charcoal palette. Clinical infographic style, editorial medical-guide polish, no pricing content.","Split-screen landscape format (1536×1024) comparing two research study design scenarios side by side. Left panel labeled 'Confounded Design' shows a simplified timeline bar where sedation, reduced activity, and decreased food intake overlap with a red warning callout reading 'Sedation Mimics Treatment Effect'. Right panel labeled 'Controlled Design' shows a parallel timeline with separate measurement tracks for sleep quality, appetite peptides (ghrelin, leptin, GLP-1), and caloric intake, each with distinct color-coded arrows and short callout labels. Clean white background, blue and amber palette, numbered step annotations, editorial scientific illustration style.","Isometric illustration landscape format (1536×1024) depicting the metabolic signaling cascade relevant to sleep-peptide interactions in appetite research. Central visual: a stylized brain emitting sleep-wave arcs that connect downward to two labeled peptide nodes, 'Ghrelin (rises with poor sleep)' on the left and 'Leptin (falls with poor sleep)' on the right. A third node at the bottom is labeled 'GLP-1 / Incretin Axis' with a dashed arrow from a peptide vial icon representing retatrutide research context. Small annotation bubbles indicate 'Trazodone: indirect pathway only'. Warm amber and deep teal gradient background, clean isometric vector style, editorial quality."]

Fewer than 10 controlled human studies have directly measured how trazodone affects appetite-regulating peptides such as ghrelin, leptin, or GLP-1, yet the drug is prescribed to millions for sleep. That gap creates a real methodological hazard for researchers studying appetite compounds like retatrutide or tesofensine alongside trazodone: sedation and sleep changes can quietly masquerade as treatment effects.
Understanding trazodone and peptide appetite studies, separating sedation, sleep, food intake, and metabolic signaling, is essential for any team designing or interpreting trials where multiple variables converge on eating behavior.
Key Takeaways
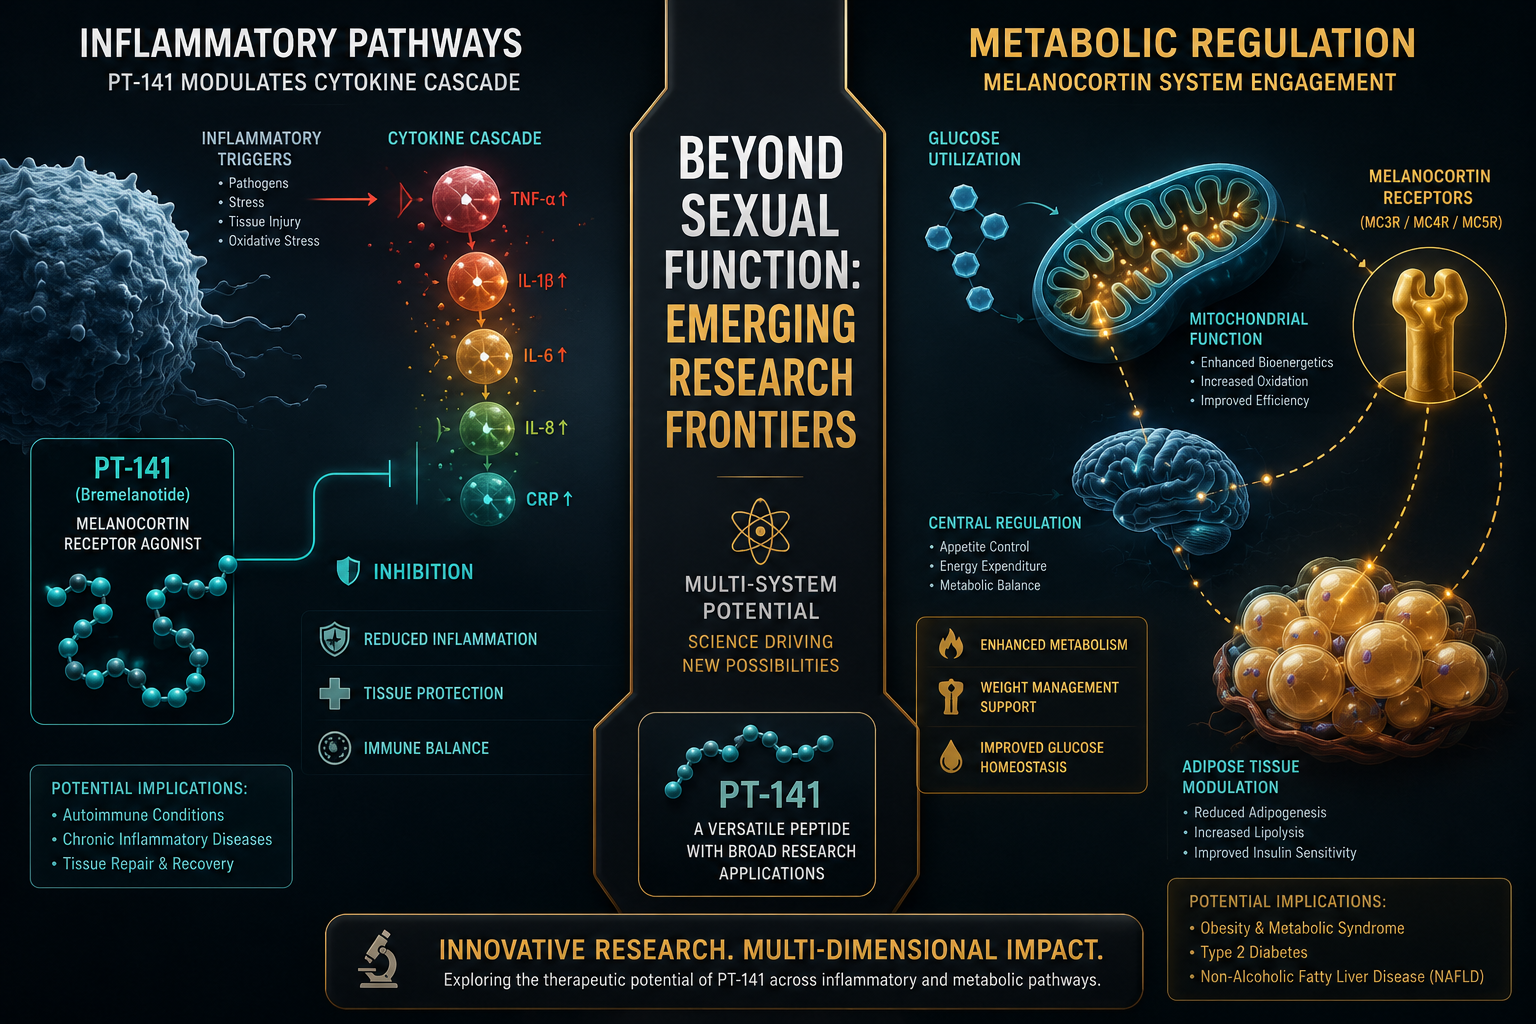
- Trazodone is considered largely weight-neutral; appetite reduction is an infrequent, tolerability-driven side effect, not a therapeutic mechanism.
- Sedation and decreased appetite are independent adverse effects, but both can distort food-intake endpoints in appetite peptide research.
- Sleep normalization caused by trazodone may indirectly shift ghrelin and leptin levels, creating confounded metabolic readouts.
- No robust human studies directly measure trazodone's impact on GLP-1, insulin, or ghrelin under controlled feeding conditions as of 2026.
- Researchers using appetite-active compounds alongside trazodone must build in sleep-quality and sedation controls to isolate true peptide effects.
How Trazodone Works and Why It Matters for Appetite Research
Trazodone is a serotonin antagonist and reuptake inhibitor (SARI). Its two most clinically relevant properties are histamine H1 receptor blockade, which drives sedation, and serotonin modulation, which influences mood and, theoretically, satiety signaling. Current regulatory labeling and clinical guidance consistently classify trazodone as weight-neutral, with appetite changes listed as infrequent. Expert summaries of antidepressant-related metabolic disturbances place trazodone among the lowest-risk agents for weight gain, some data even suggest a marginal lean toward weight loss.
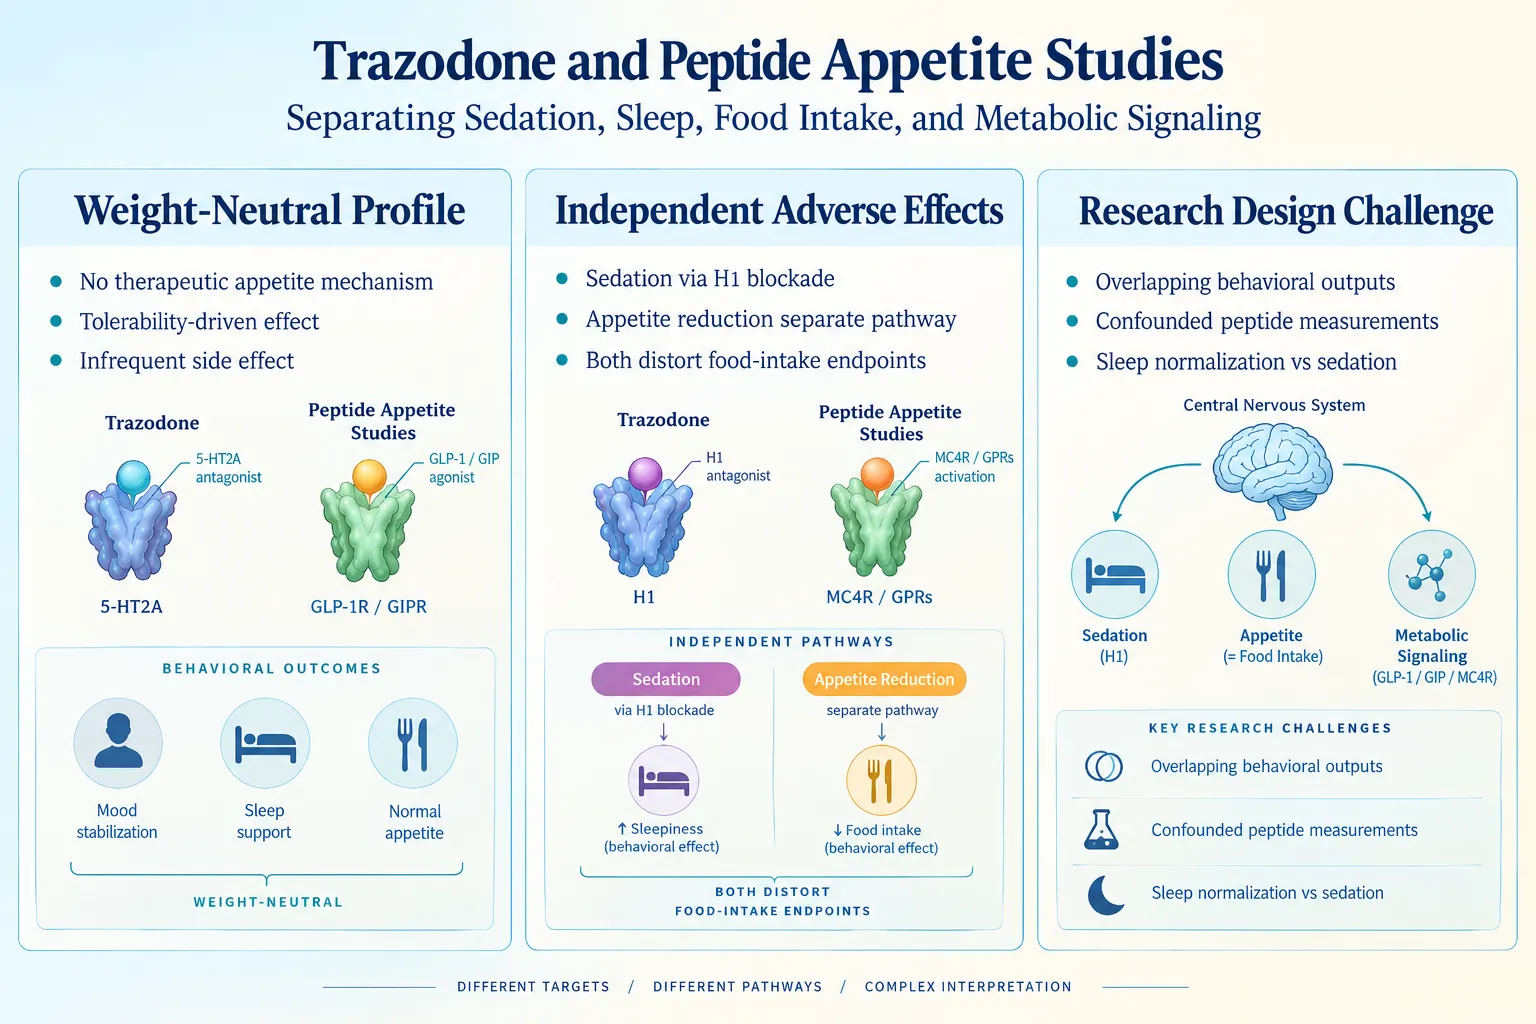
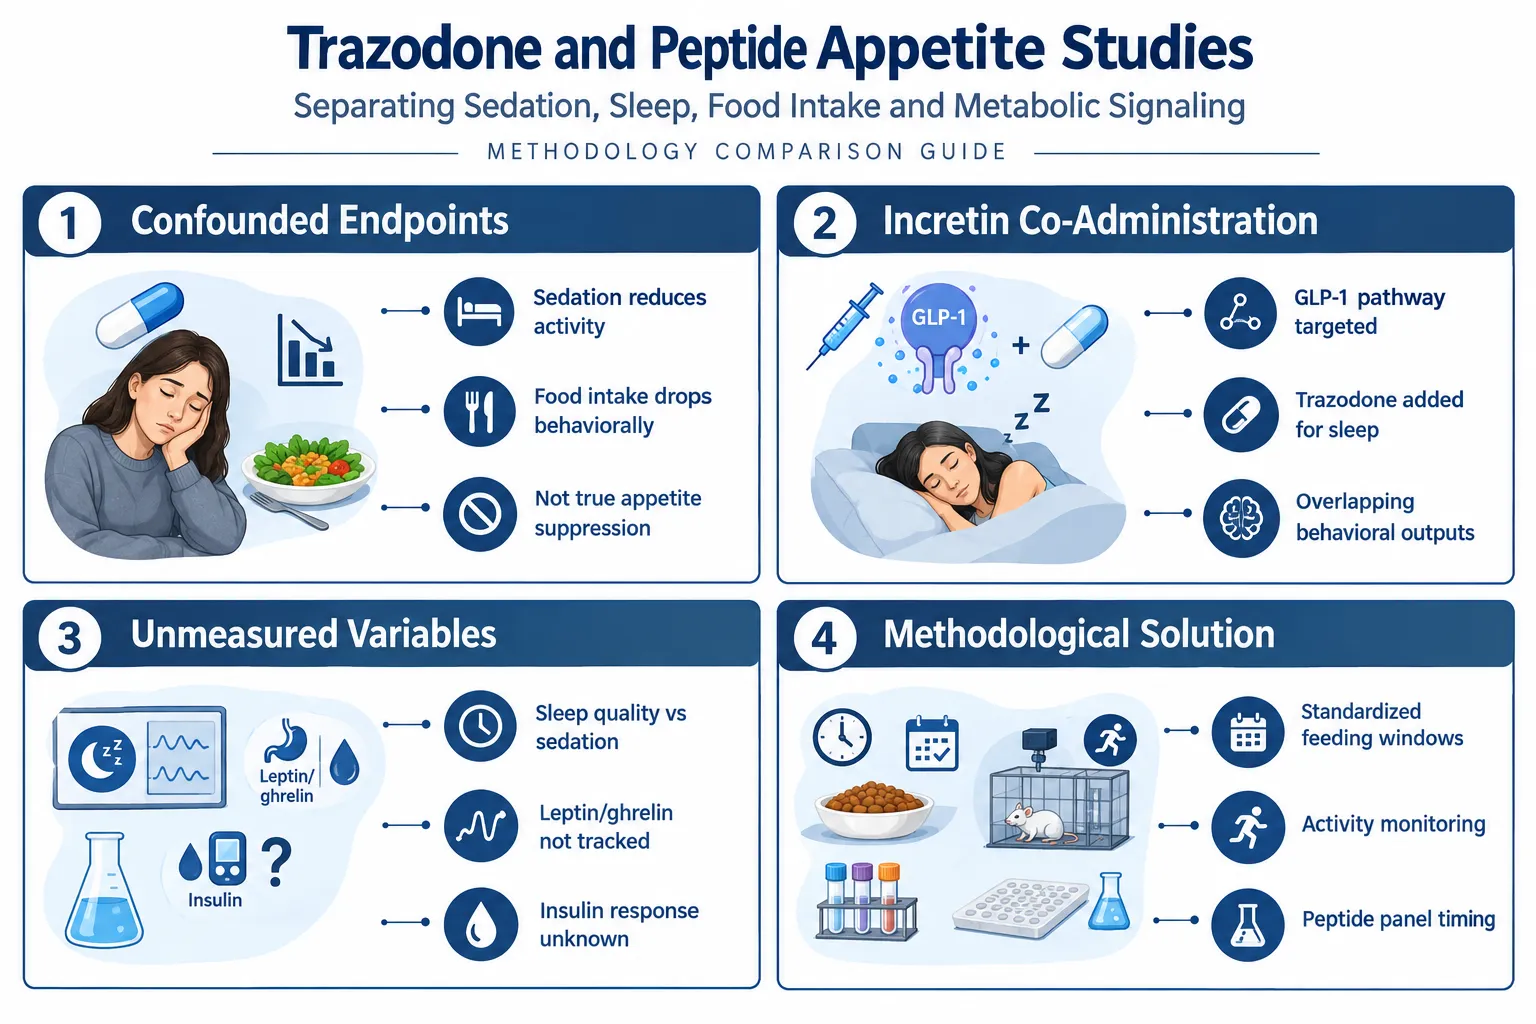
For peptide appetite studies, this creates a subtle problem. A participant taking trazodone for insomnia may eat less not because a study compound is working, but because they are sedated, less physically active, or simply less motivated to prepare meals. These behavioral suppressors of caloric intake look identical to a genuine peptide-driven reduction in hunger on a food diary or calorie-count endpoint.
Key pharmacological actions relevant to appetite research:
| Mechanism | Direct Effect | Potential Appetite Impact |
|---|---|---|
| H1 blockade | Sedation, drowsiness | Reduced meal frequency |
| Serotonin reuptake inhibition | Mood stabilization | Modest satiety modulation |
| Alpha-1 adrenergic blockade | Orthostatic effects | Nausea, indirect intake reduction |
| Prolactin elevation | Hormonal shift | Minor; not clinically quantified |
Study Design Flaws: When Sedation Mimics Treatment in Trazodone and Peptide Appetite Studies
The central methodology challenge in trazodone and peptide appetite studies, separating sedation, sleep, food intake, and metabolic signaling, is that sedation and appetite suppression share overlapping behavioral outputs. When researchers pair trazodone with compounds targeting the incretin axis, such as GLP-3R peptide research variants, the sedation signal can inflate apparent efficacy on intake endpoints.
Three specific confounds deserve attention:
- Reduced locomotor activity. Sedated subjects move less, burn fewer calories, and may underreport hunger because they are asleep or low-arousal during typical meal windows.
- Nausea overlap. Both trazodone and GLP-1-class peptides can produce nausea. Without separate adverse-event tracking, nausea-driven intake reduction is falsely attributed to appetite peptide activity.
- Sleep improvement altering baseline peptides. Short sleep is well-established to reduce leptin and elevate ghrelin, increasing hunger. If trazodone normalizes sleep architecture, it will partially reverse that pattern, lowering ghrelin and raising leptin, independently of any metabolic compound under study.
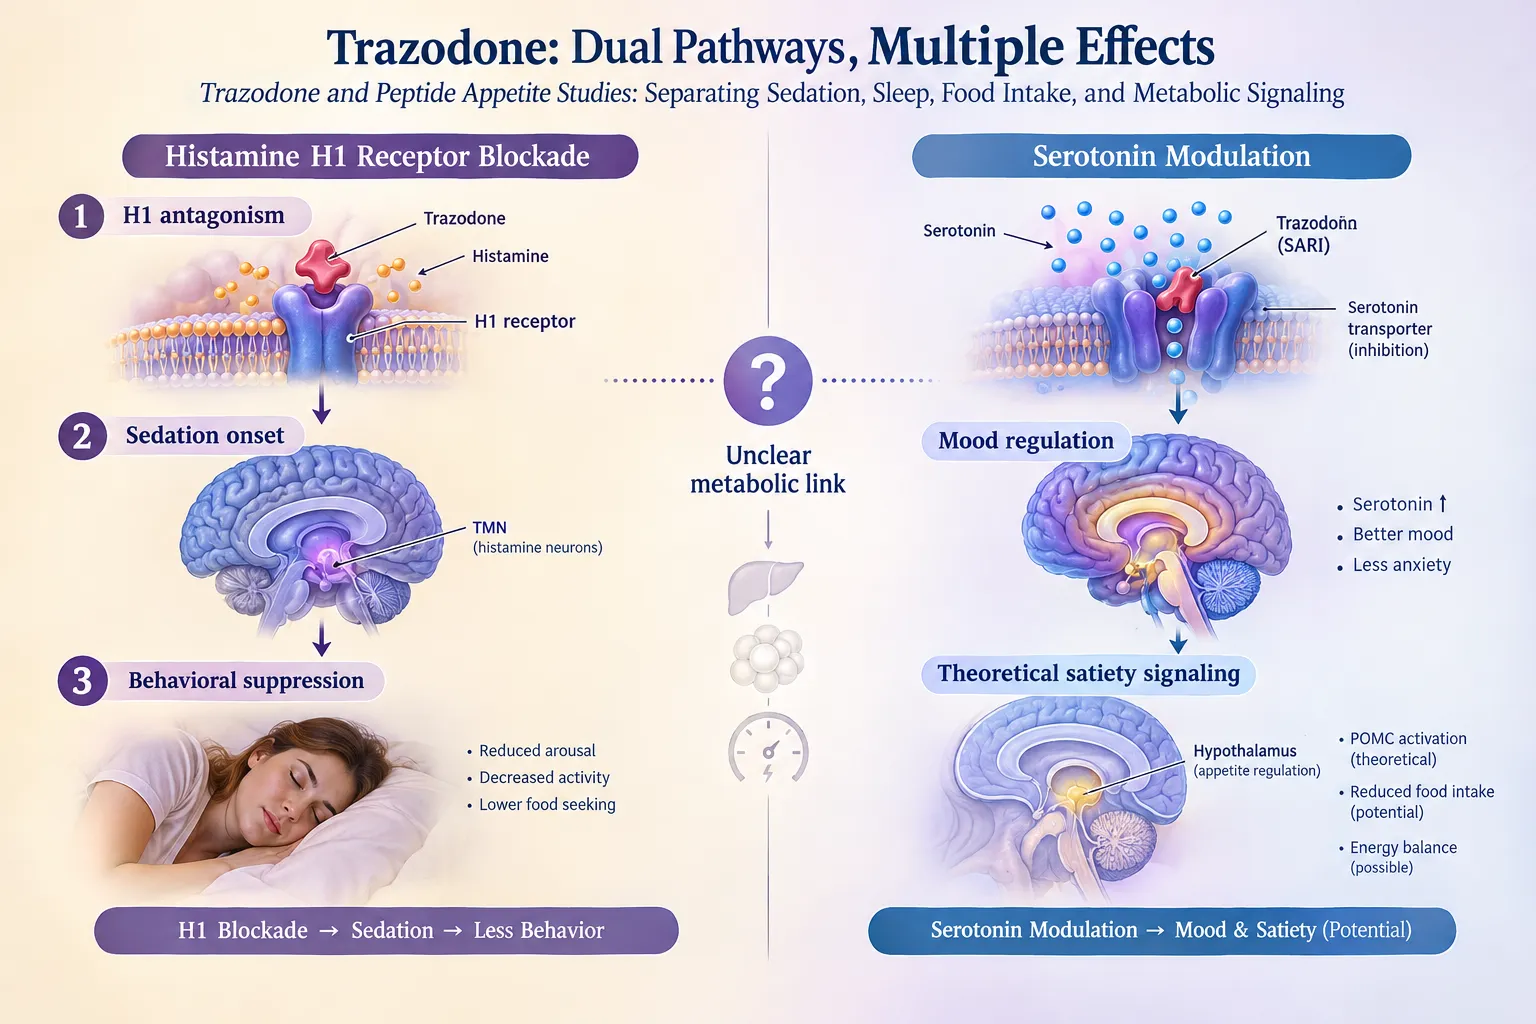
"The most likely pathway by which trazodone touches metabolic peptides is indirect, through sleep normalization rather than direct receptor-level appetite signaling."
Researchers using GLP-3R 30mg peptide formulations in combination protocols must account for baseline sleep quality in both arms of a study. Omitting actigraphy or validated sleep-quality instruments leaves an uncontrolled variable that can shift ghrelin readouts by 15-20% between groups without any pharmacological intervention from the study compound.
For reference standards in peptide work, ensuring compound identity is foundational; resources on Bachem and reference standards for peptide benchmarks outline why purity verification precedes any mechanistic interpretation.
Metabolic Signaling Gaps and the Path Forward
The honest summary of the literature in 2026 is blunt: virtually no controlled human trials have isolated trazodone's effects on leptin, ghrelin, insulin, or GLP-1 under standardized feeding conditions. That is a significant data gap given how commonly trazodone co-prescriptions appear in populations enrolled in metabolic and weight-loss studies.
What researchers do know supports a working model with three tiers:
- Tier 1, Confirmed: Trazodone causes sedation and, independently, infrequent appetite decrease as a tolerability side effect.
- Tier 2, Mechanistically plausible: Sleep normalization from trazodone secondarily shifts ghrelin and leptin in a hunger-reducing direction.
- Tier 3, Speculative: Any direct trazodone effect on GLP-1 secretion, insulin sensitivity, or peptide YY is uncharacterized and should not be assumed.
This tiered model has direct implications for trials pairing trazodone with compounds such as retatrutide. Researchers can explore RETA GLP-3 peptide options alongside proper methodological controls, but must treat trazodone-related sleep changes as a covariate, not a neutral background variable.
Quality controls matter equally on the peptide side. Reviewing PT-141 peptide for sale research context and QA controls illustrates how rigorous sourcing and purity documentation protect the integrity of any appetite-related protocol. Similarly, understanding peptide half-life is critical when scheduling blood draws to capture peptide-level appetite signals at biologically meaningful timepoints.
Recommended methodological safeguards:
- Include validated sleep instruments (Pittsburgh Sleep Quality Index or actigraphy) as a covariate in all food-intake analyses.
- Track sedation scores separately from hunger/satiety visual analog scales.
- Distinguish nausea-driven intake reduction from appetite peptide-driven satiety using biomarker panels (fasting ghrelin, postprandial GLP-1, leptin).
- Use matched-sedation control arms when trazodone is a concomitant medication, not just a placebo-vs-treatment design.
- Report trazodone dose and timing relative to both sleep and meal windows in all study disclosures.
Conclusion
The intersection of trazodone and peptide appetite studies demands sharper methodological discipline than most current protocols provide. Trazodone is weight-neutral and lacks a direct, characterized pathway to the appetite peptides that drive hunger and satiety. However, its sedating properties and its capacity to normalize sleep architecture mean it can shift caloric intake and peptide baselines through indirect routes that look like pharmacological efficacy in a poorly controlled trial.
Actionable steps for researchers and study designers:
- Map trazodone's sedation burden quantitatively before treating food-intake data as a clean endpoint.
- Treat sleep quality as a primary covariate, not a footnote, in any metabolic peptide trial.
- Recognize the current data gap and design studies that specifically measure ghrelin, leptin, and GLP-1 when trazodone is a concomitant or active comparator.
- Consult reference-standard documentation and GLP peptide sourcing resources to ensure compound integrity before drawing mechanistic conclusions.
Future research will most productively focus on trazodone's role in metabolic health through the sleep-normalization pathway, not as a direct appetite modulator. Getting that framing right protects both the scientific validity of appetite peptide trials and the clinical relevance of their findings.