Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: retatrutide clinical trial

Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions

Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions

September 26, 2026/0 Comments/in Uncategorized/by

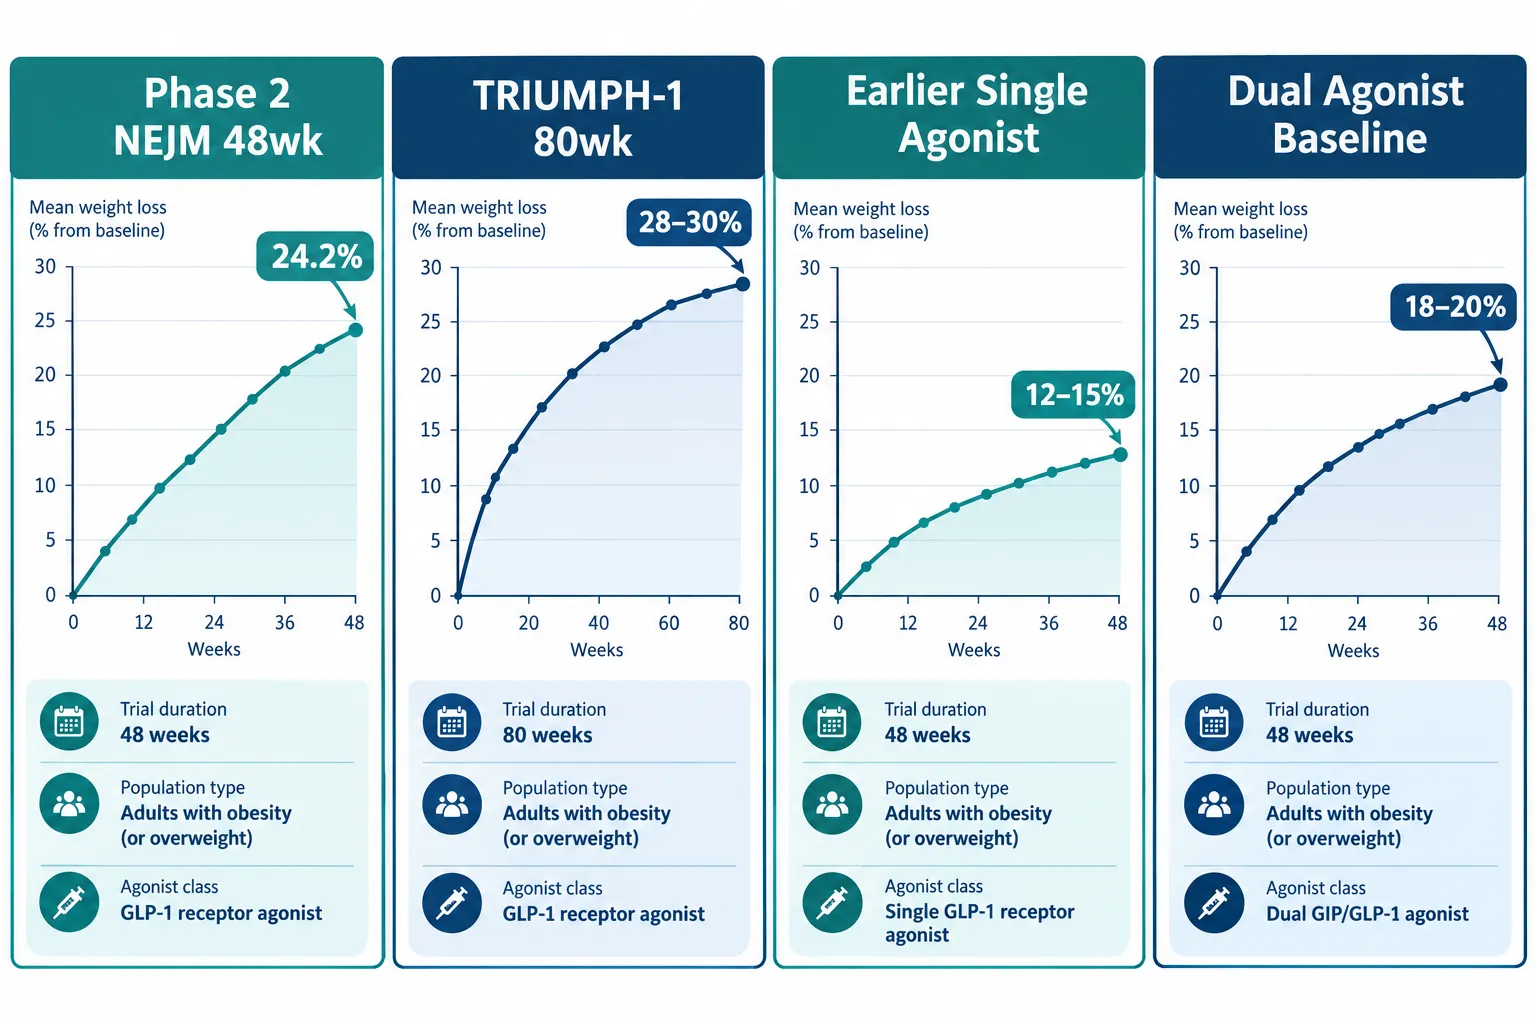
A single Phase 2 result, 24.2% mean body weight loss at 48 weeks, repositioned retatrutide as a potential turning point in obesity pharmacotherapy. Now, with the TRIUMPH program delivering Phase 3 data in 2026 and an FDA submission planned for early 2027, the research community faces a more demanding challenge: comparing these new numbers against earlier obesity models without letting headline figures obscure methodological differences that matter enormously.

Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions is not simply a question of which drug produces a bigger number. It is a question of whether the numbers are even measuring the same thing across studies.

Key Takeaways

  • Retatrutide is a triple agonist (GLP-1, GIP, glucagon receptors), making direct comparisons to earlier single- or dual-agonist trials structurally complex.
  • TRIUMPH-1 reports up to 28-30% weight loss over 80 weeks, but population composition, baseline BMI, and trial duration differ from earlier benchmarks.
  • Estimand frameworks, dose escalation schedules, and completeness of adverse-event reporting vary significantly across generations of obesity trials.
  • Glycemic endpoints (A1C reduction) in TRIUMPH-2 require careful alignment with earlier diabetic-population studies before conclusions are drawn.
  • A transparent comparison framework covering at least seven variables is essential before any cross-trial efficacy claim holds scientific weight.

Why the Comparison Problem Is Harder Than It Looks
Why the Comparison Problem Is Harder Than It Looks

The excitement around retatrutide is understandable. The TRIUMPH-1 trial, targeting non-diabetic adults with obesity or overweight, reported weight reductions approaching 28-30% over 80 weeks, figures that have drawn frequent comparisons to bariatric surgery outcomes. TRIUMPH-2 extended the analysis to people with type 2 diabetes, and TRIUMPH-3 enrolled participants with severe obesity and established cardiovascular disease. A global registration trial completed enrollment in late 2025, broadening the population further.

Earlier obesity pharmacotherapy trials, including those for semaglutide and tirzepatide, ran for 68 weeks in many pivotal designs, enrolled populations with somewhat different baseline BMI distributions, and used dose escalation schedules that do not map cleanly onto retatrutide's protocol. Researchers exploring retatrutide clinical trial data will quickly notice that the surface-level weight-loss percentages are not the only variable worth examining.

Seven variables that demand alignment before cross-trial comparison:

Variable Why It Matters
Population baseline BMI Higher baseline BMI inflates absolute kg lost
Trial duration (weeks) Longer trials favor plateau-resistant compounds
Estimand framework Defines how dropouts and discontinuations are handled
Dose escalation schedule Steeper escalation can accelerate early weight loss
Completeness of AE reporting Affects tolerability profile comparisons
Glycemic endpoints (A1C) Critical for diabetic-population sub-analyses
Completers vs ITT analysis Changes the denominator and the headline figure

"A 30% weight loss figure means very little in isolation. The population, the protocol, and the statistical framework are the context that gives the number meaning."


Mechanism Differences That Complicate Direct Comparisons
Mechanism Differences That Complicate Direct Comparisons

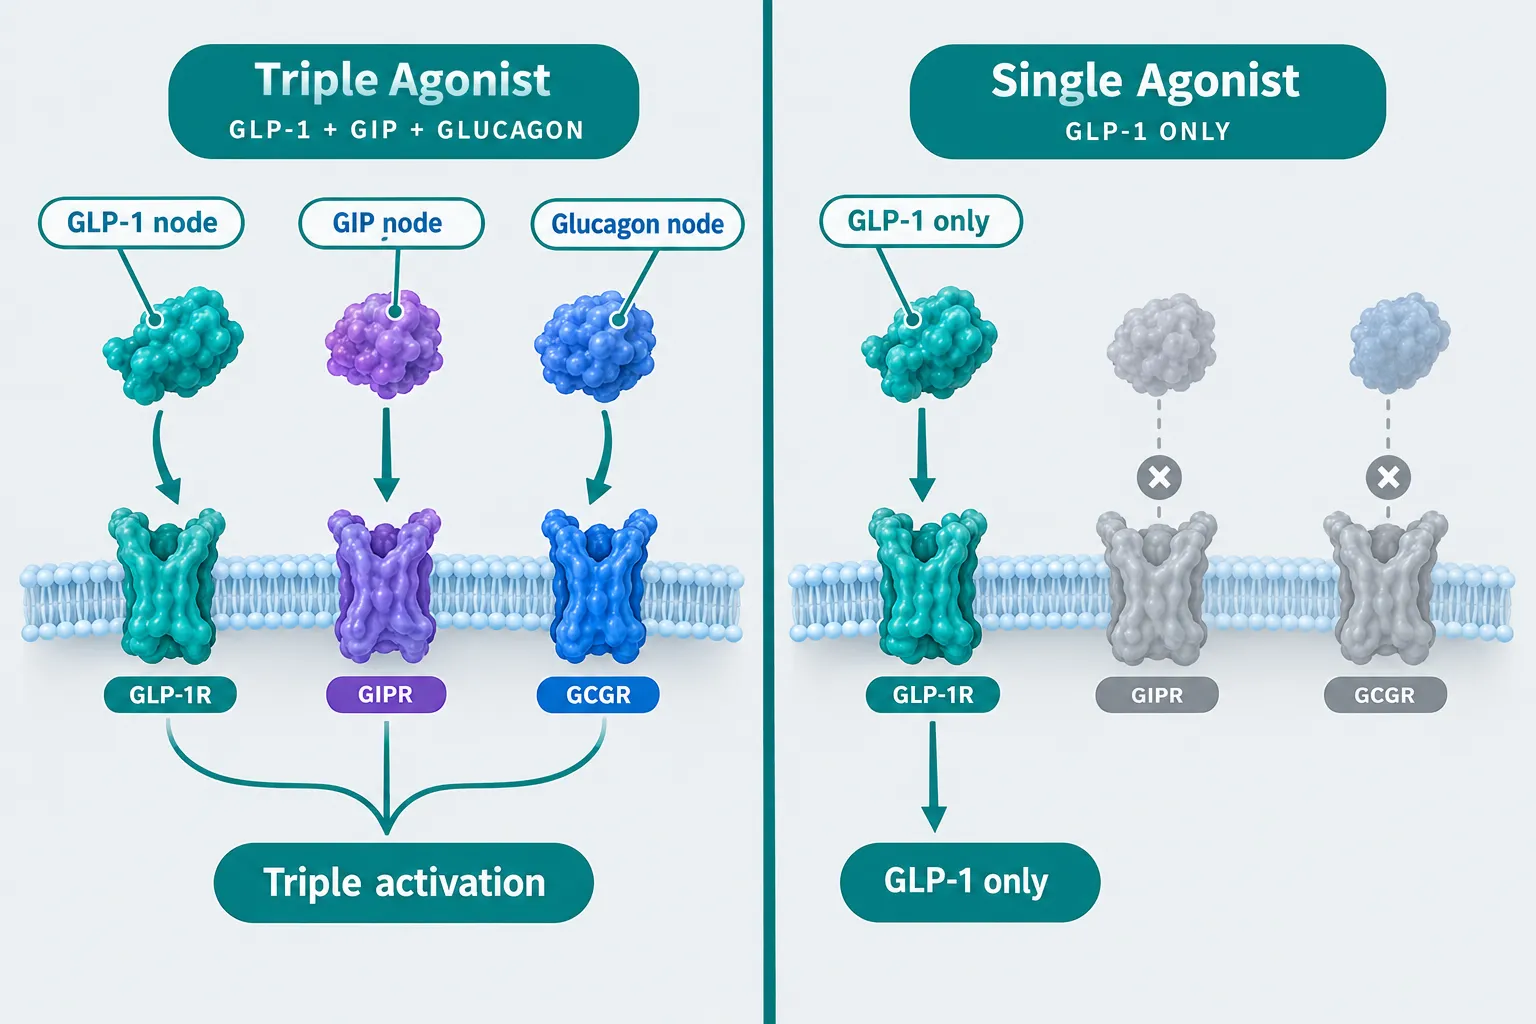
Retatrutide is a triple agonist, activating GLP-1, GIP, and glucagon receptors simultaneously. Earlier approved agents in this space are single agonists (GLP-1 only) or dual agonists (GLP-1 and GIP). This mechanistic distinction is not merely academic, it directly affects which endpoints are most informative and which adverse-event profiles are expected.

Glucagon receptor activation drives additional energy expenditure and lipolysis pathways that are absent in earlier models. This means that comparing retatrutide's weight-loss magnitude against a GLP-1 monotherapy trial without accounting for the additional metabolic burden on participants is methodologically incomplete. Researchers interested in the GLP-3 Reta product tag context will recognize that the triple-agonist classification is central to understanding why the efficacy signal appears larger.

Key mechanistic comparison points:

  • GLP-1 component: Shared with earlier agents; allows partial endpoint alignment on nausea, satiety, and gastric motility outcomes.
  • GIP component: Shared with tirzepatide; permits limited dual-agonist comparison, but retatrutide's GIP binding affinity differs.
  • Glucagon component: Unique to retatrutide in this class; drives hepatic fat reduction and thermogenesis outcomes not tracked in earlier trial designs.

For researchers also examining peptides with distinct metabolic profiles, the Tesamorelin science and sourcing overview offers a useful reference point for understanding how growth-hormone-releasing peptides address visceral fat through a separate mechanism, underscoring why mechanism-first framing matters in any comparative analysis.


Building a Transparent Framework for Cross-Trial Analysis
Building a Transparent Framework for Cross-Trial Analysis

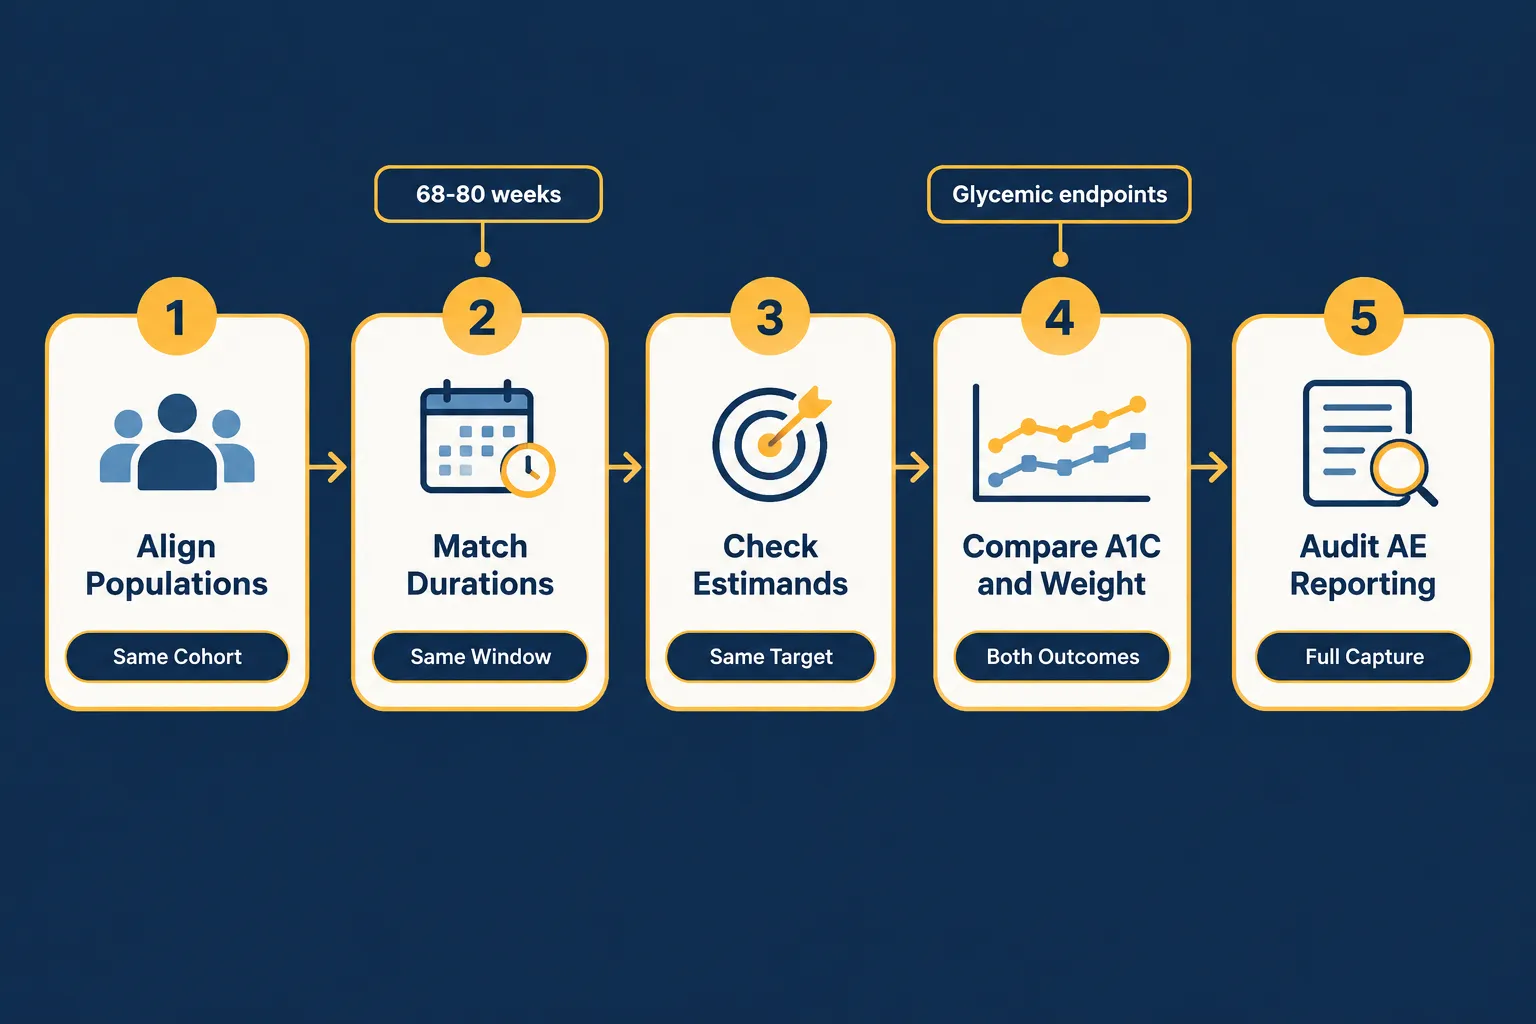
Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions comes down to a structured, reproducible framework rather than selective headline matching. The following steps reflect best practice for cross-generational obesity trial comparison.

Step 1, Align populations. Confirm that baseline BMI, diabetes status, cardiovascular comorbidity burden, and geographic distribution are comparable. TRIUMPH-3's cardiovascular-disease population is not equivalent to a general overweight cohort.

Step 2, Match or adjust for duration. TRIUMPH-1's 80-week window exceeds the 68-week standard used in several earlier pivotal trials. Annualized weight-loss rates provide a more honest cross-trial metric than raw endpoint figures.

Step 3, Examine estimands explicitly. The treatment policy estimand (which includes all participants regardless of discontinuation) and the hypothetical estimand (which models outcomes assuming full adherence) produce materially different results. Earlier trials varied in which they pre-specified as primary.

Step 4, Compare A1C and glycemic outcomes in matched populations. TRIUMPH-2 data on weight and glycemic outcomes in type 2 diabetes must be benchmarked only against earlier trials that enrolled comparable diabetic populations with similar baseline A1C ranges.

Step 5, Audit adverse-event completeness. Gastrointestinal adverse events are consistently reported across generations, but cardiovascular safety signals, injection-site reactions, and lean mass loss data have not been uniformly collected. Retatrutide's glucagon component introduces a hepatic safety dimension that earlier single-agonist trial protocols did not systematically monitor.

Researchers building stacks or combination protocols may also find value in reviewing the IPA Sermorelin stack research resource for context on how multi-peptide frameworks are evaluated in research settings, and the SS-31 mitochondrial research tag for parallel work on metabolic and mitochondrial endpoints that may become relevant as retatrutide's full metabolic profile is characterized.

For researchers seeking the compound itself for preclinical work, the Reta 20mg product page provides sourcing details relevant to laboratory use.


Conclusion

The TRIUMPH program represents a genuine advance in obesity pharmacotherapy research, and the 2026 data deserve serious scientific attention. But the value of that data depends entirely on how carefully it is contextualized against earlier obesity models.

Actionable next steps for researchers:

  1. Build a comparison table that explicitly lists population baseline characteristics, trial duration, estimand type, and primary endpoint definition for each study being compared.
  2. Separate efficacy comparisons by population subgroup, non-diabetic, type 2 diabetes, and high-cardiovascular-risk cohorts require distinct reference studies.
  3. Request or locate full adverse-event appendices, not just summary tables, before drawing tolerability conclusions.
  4. Apply annualized weight-loss rates as a normalized cross-trial metric rather than relying on raw endpoint percentages.
  5. Track the FDA submission timeline (currently planned for Q1 2027) and review any agency briefing documents for additional population and estimand disclosures.

Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions is ultimately a call for methodological discipline. The numbers are impressive, but the framework used to evaluate them will determine whether the conclusions hold.


https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-2026-trial-data-vs-earlier-obesity-models-what-researchers-should-co.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:05:022026-09-26 13:05:02Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions

Tag Archive for: retatrutide clinical trial

GLP-3 Retatrutide vs Traditional GLP-1 Agonists: Mechanisms, Early Data, and Research-Only Use Cases

GLP-3 Retatrutide vs Traditional GLP-1 Agonists: Mechanisms, Early Data, and Research-Only Use Cases

June 3, 2026/0 Comments/by Pure Tested

A single peptide producing nearly 29% mean body weight loss in a clinical trial is not a headline most metabolic researchers expected to see this decade. Yet that is precisely what early data from retatrutide's Phase 3 program suggests. Understanding the comparison of GLP-3 Retatrutide vs Traditional GLP-1 Agonists: Mechanisms, Early Data, and Research-Only Use Cases requires looking closely at receptor biology, trial outcomes, and the strict research boundaries that currently govern this compound.

Key Takeaways

  • Retatrutide is a triple agonist activating GLP-1, GIP, and glucagon receptors simultaneously, while classic GLP-1 agents target only one receptor.
  • Phase 2 and early Phase 3 data show weight reductions of 24.2% to 28.7%, surpassing results seen with semaglutide or tirzepatide.
  • Retatrutide reduced liver fat by up to 82.4% in clinical studies, pointing to broad metabolic utility.
  • As of 2026, retatrutide is not FDA-approved and is designated for laboratory and research use only.
  • An FDA filing is anticipated between 2026 and 2027, making this a critical period for preclinical researchers to build foundational knowledge.

Receptor Mechanisms: How Retatrutide Differs from Classic GLP-1 Agonists

Receptor Mechanisms: How Retatrutide Differs from Classic GLP-1 Agonists

Traditional GLP-1 receptor agonists such as semaglutide work by mimicking the incretin hormone GLP-1. This single-receptor approach suppresses appetite, slows gastric emptying, and improves insulin secretion. The results are clinically meaningful, but the mechanism is inherently limited to one signaling pathway.

Retatrutide expands that model significantly. It activates three distinct receptors:

Receptor Primary Role
GLP-1 Appetite suppression, delayed gastric emptying
GIP Enhanced insulin secretion, lipid metabolism
Glucagon Increased energy expenditure, fat oxidation

This triple-agonist design means the compound addresses energy balance from multiple angles at once. The glucagon receptor component is particularly notable. While glucagon is classically associated with raising blood glucose, its activation in a balanced incretin context appears to drive thermogenesis and fat oxidation without destabilizing glycemic control.

Cryo-electron microscopy studies have mapped exactly how retatrutide engages all three receptor types at the molecular level, providing a structural explanation for its activity profile. For researchers exploring the broader GLP-1 generations overview, this mechanistic leap from single to triple agonism represents a defining shift in incretin pharmacology.

Tirzepatide, a dual GLP-1/GIP agonist, sits between semaglutide and retatrutide on this spectrum. Retatrutide's additional glucagon receptor activation is the primary differentiator that researchers believe accounts for its superior efficacy signals in early trials.


Early Clinical Data: What the Trial Numbers Show

Early Clinical Data: What the Trial Numbers Show

The numbers from retatrutide's clinical program are difficult to ignore. In a Phase 2 trial published in the New England Journal of Medicine, participants receiving the 12 mg dose achieved a mean body weight reduction of 24.2% at 48 weeks. That figure exceeded the weight loss benchmarks set by both semaglutide and tirzepatide in comparable timeframes.

Preliminary data from the Phase 3 TRIUMPH-4 trial pushed that figure further. At 68 weeks, the mean body weight loss reached 28.7%, the highest reduction recorded in an obesity trial to date.

Beyond weight, the metabolic data is equally compelling:

  • Liver fat reduction of up to 82.4%, suggesting significant potential for non-alcoholic fatty liver disease research
  • Improvements in glycemic control and lipid profiles across trial cohorts
  • Once-weekly subcutaneous dosing with a half-life of approximately 6 days, supporting practical research protocols

The side effect profile is consistent with other incretin-based compounds. Gastrointestinal effects including nausea and vomiting were the most commonly reported adverse events, which aligns with what researchers observe across the GLP-1 class.

For those tracking how body composition peptides interact with metabolic pathways, the TESA body composition research themes page offers relevant context on related investigational compounds. Similarly, researchers studying fat metabolism may find value in reviewing AOD-9604 research method notes as a complementary reference point.


Research-Only Use Cases for GLP-3 Retatrutide vs Traditional GLP-1 Agonists

Research-Only Use Cases for GLP-3 Retatrutide vs Traditional GLP-1 Agonists

As of 2026, retatrutide holds no FDA approval and is not available for commercial or clinical use outside of authorized trials. It is strictly designated for laboratory and research purposes. This boundary is not a limitation to work around; it is the appropriate framework for a compound still moving through regulatory evaluation.

Within that framework, legitimate research use cases include:

  • Receptor binding studies examining triple-agonist pharmacodynamics
  • In vitro metabolic models exploring GIP and glucagon receptor co-activation
  • Preclinical obesity models comparing retatrutide's efficacy signals against established GLP-1 benchmarks
  • Liver health investigations given the striking hepatic fat reduction data

Researchers building metabolic study panels may also find it useful to explore cagrilintide synergy with GLP-1 as a complementary area of investigation, since amylin-GLP-1 combinations represent another emerging research direction. For broader metabolic and longevity research themes, the GLP-3 Reta incretin research themes resource provides a structured overview of where the science currently stands.

Researchers interested in how mitochondrial function intersects with metabolic peptide research can also reference MOTS-c mitochondrial peptide research for related mechanistic context.

An FDA filing is anticipated between 2026 and 2027. Until that process concludes, all use must remain within certified research environments with appropriate oversight.


Conclusion

The comparison of GLP-3 Retatrutide vs Traditional GLP-1 Agonists: Mechanisms, Early Data, and Research-Only Use Cases reveals a compound that is mechanistically distinct and clinically promising. Its triple-receptor design addresses metabolic dysfunction through pathways that single and dual agonists cannot reach simultaneously. The trial data, while still maturing, places retatrutide ahead of any previously studied obesity intervention by weight-loss magnitude.

Actionable next steps for researchers in 2026:

  1. Review the Phase 2 NEJM publication and TRIUMPH-4 preliminary data to establish baseline familiarity with the efficacy and safety signals.
  2. Map retatrutide's receptor pharmacology against your existing GLP-1 or dual-agonist research models to identify where triple agonism adds mechanistic value.
  3. Ensure all procurement and use of retatrutide complies strictly with research-only designations and institutional oversight requirements.
  4. Monitor FDA filing developments expected in the 2026-2027 window, as regulatory milestones will reshape the research landscape quickly.

The science is moving fast. Researchers who build foundational knowledge now will be best positioned to interpret and apply what comes next.


https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GLP-3-Retatrutide-vs-Traditional-GLP-1-Agonists-Mechanisms-Early-Data-and-Research-Only-Use-Cases.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-03 13:04:222026-07-20 15:04:12GLP-3 Retatrutide vs Traditional GLP-1 Agonists: Mechanisms, Early Data, and Research-Only Use Cases
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top