Evaluating Antiemetic Protocols in Incretin Research: Ondansetron Mechanisms During GLP-3 Retatrutide Administration
Nausea affects more than 40% of participants in high-dose retatrutide arms during Phase 2 trials, a rate that places gastrointestinal (GI) tolerability at the center of every research design decision. As investigators push toward maximizing metabolic efficacy with this potent multi-incretin agonist, evaluating antiemetic protocols in incretin research, including the role of ondansetron mechanisms during GLP-3 retatrutide administration, has become a critical and underexplored frontier.
Key Takeaways
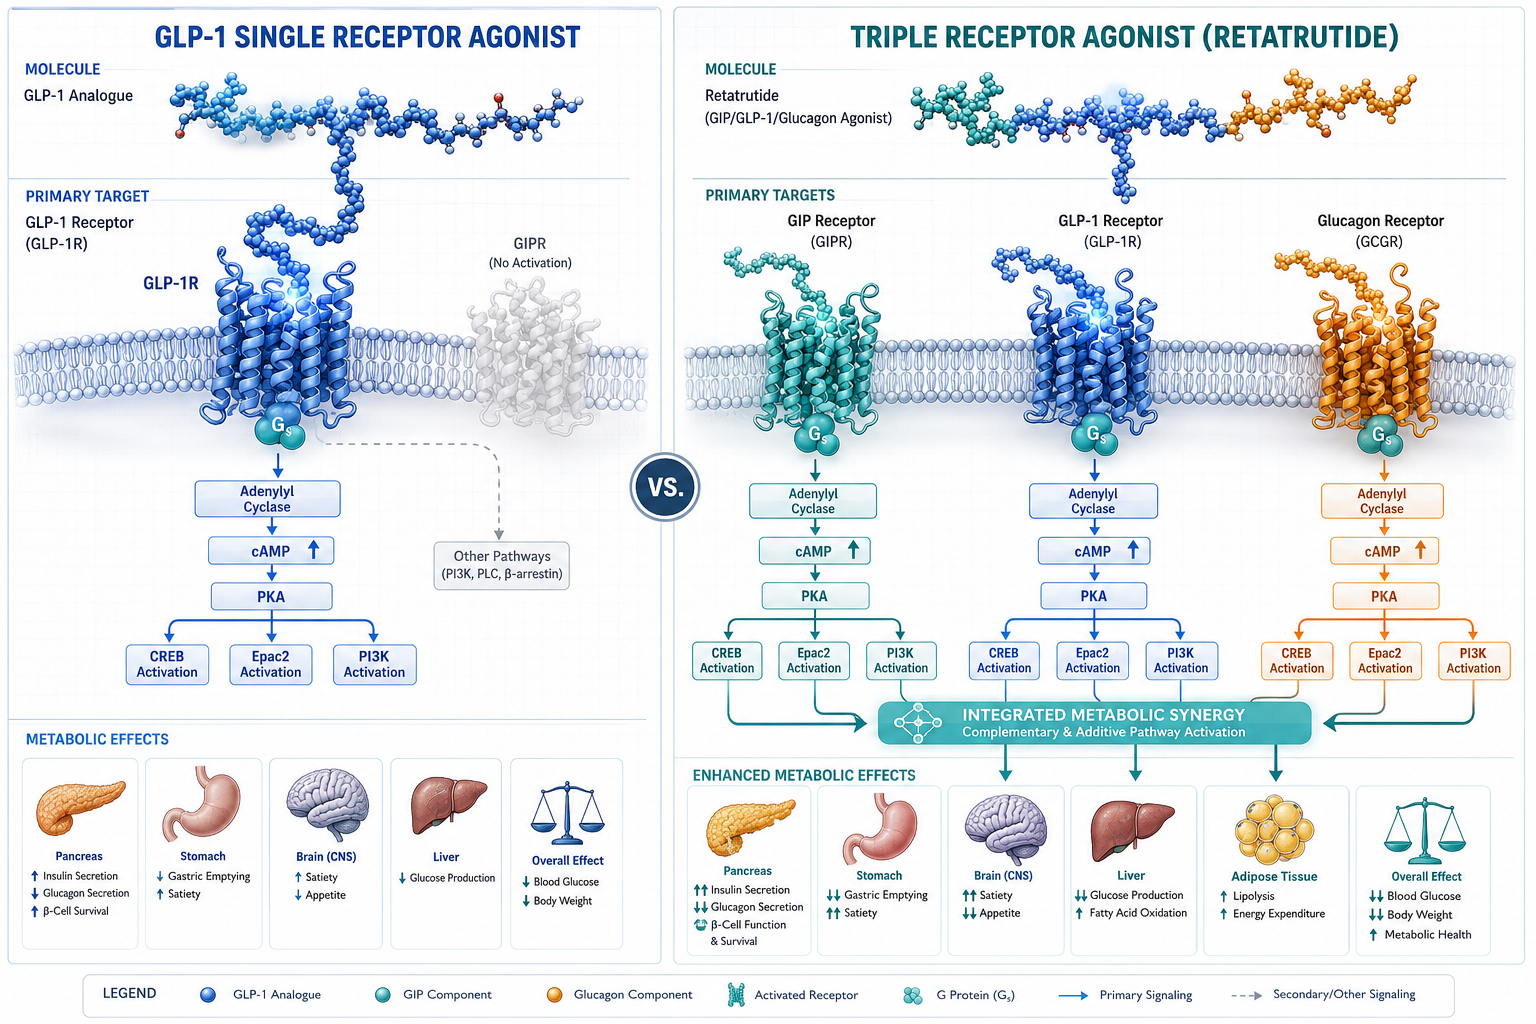
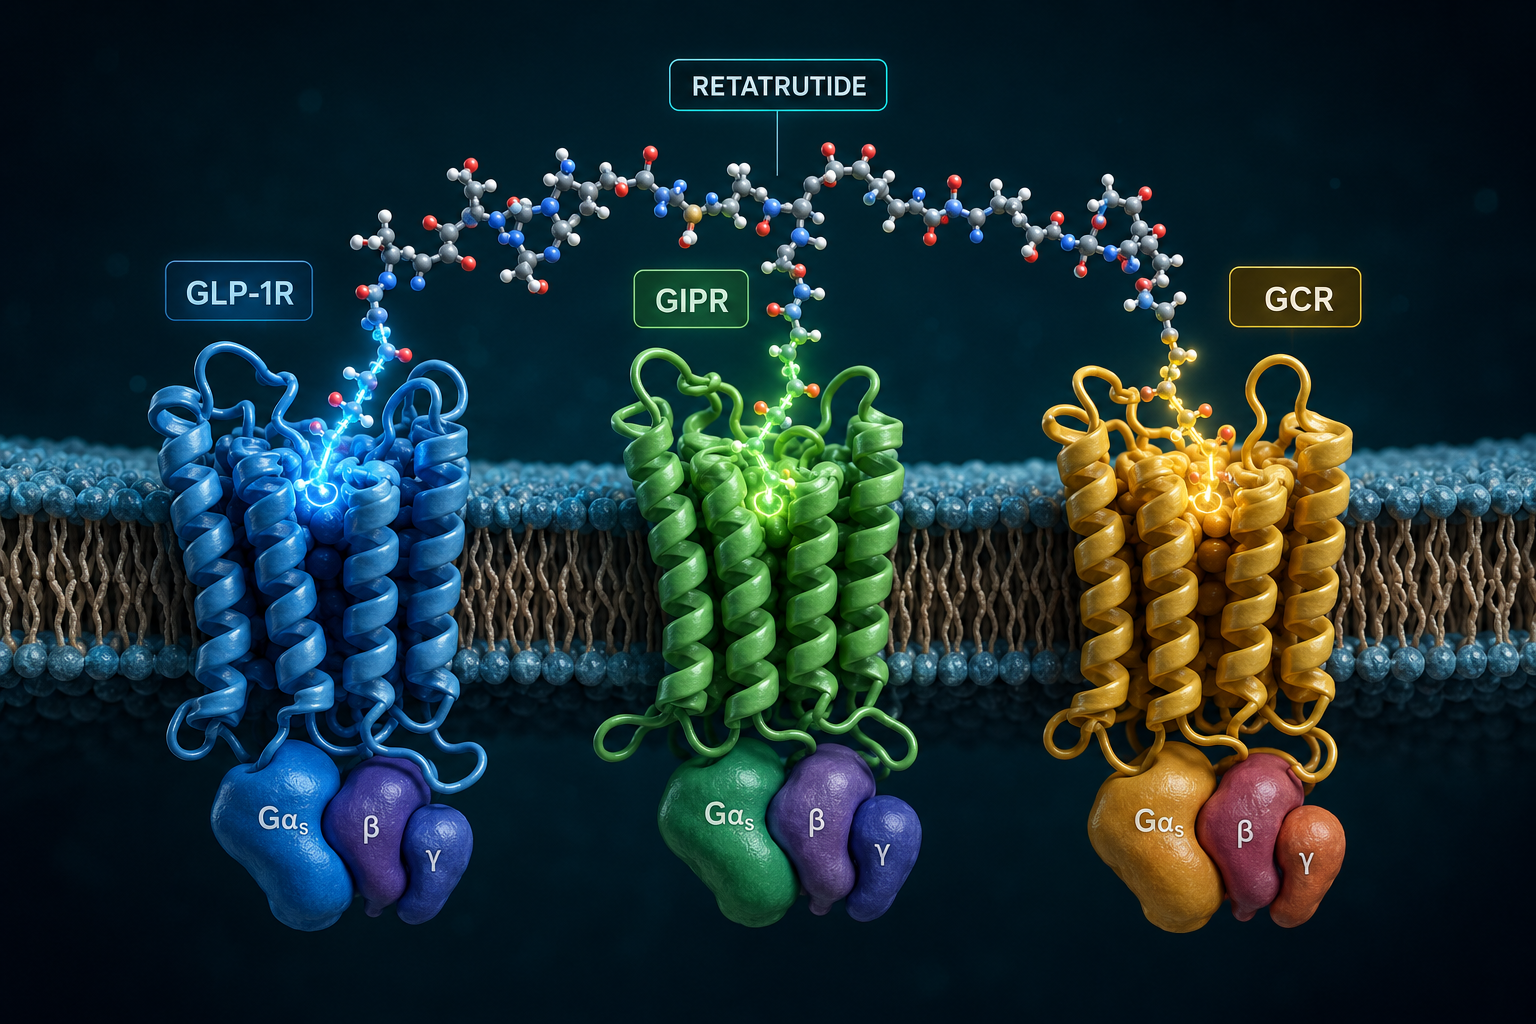
- Retatrutide (LY3437943) is a triple incretin agonist targeting GLP-1, GIP, and glucagon receptors, producing dose-dependent GI side effects.
- Nausea and vomiting rates in high-dose retatrutide cohorts are among the highest observed in the incretin drug class.
- Ondansetron, a selective 5-HT3 receptor antagonist, targets both central and peripheral serotonin pathways implicated in incretin-induced emesis.
- No formal ondansetron-specific antiemetic protocols have been published for retatrutide trials as of 2026; current management relies on dose titration.
- Structured antiemetic research protocols represent a significant opportunity to improve participant retention and trial outcomes.
Understanding Retatrutide and Its GI Burden
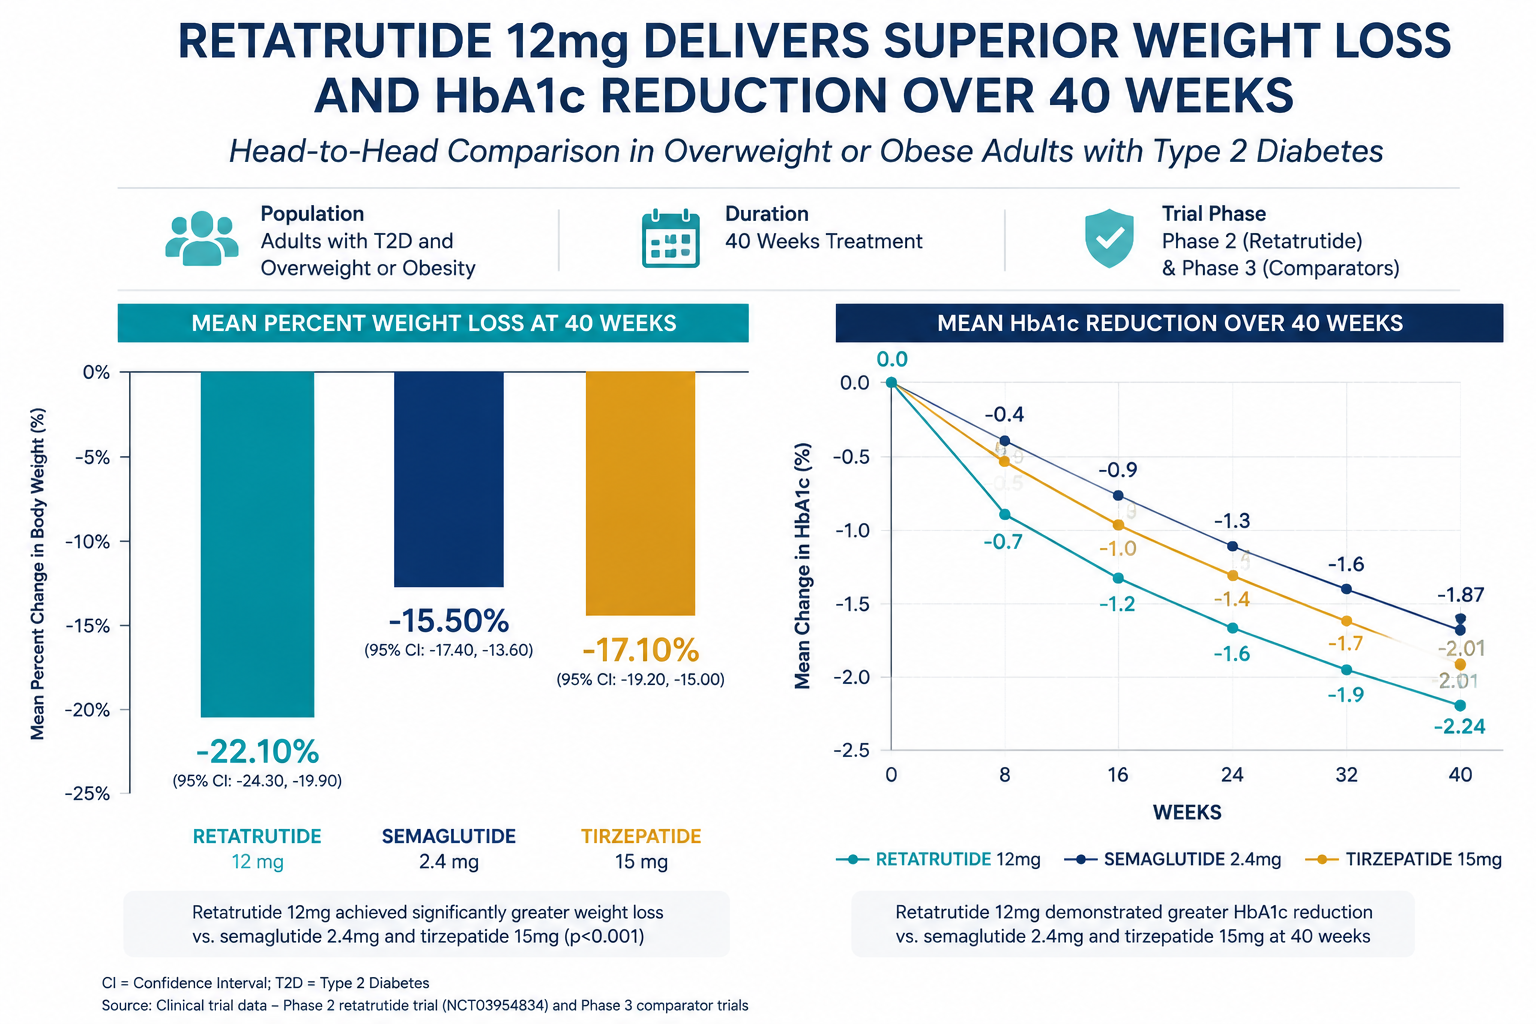
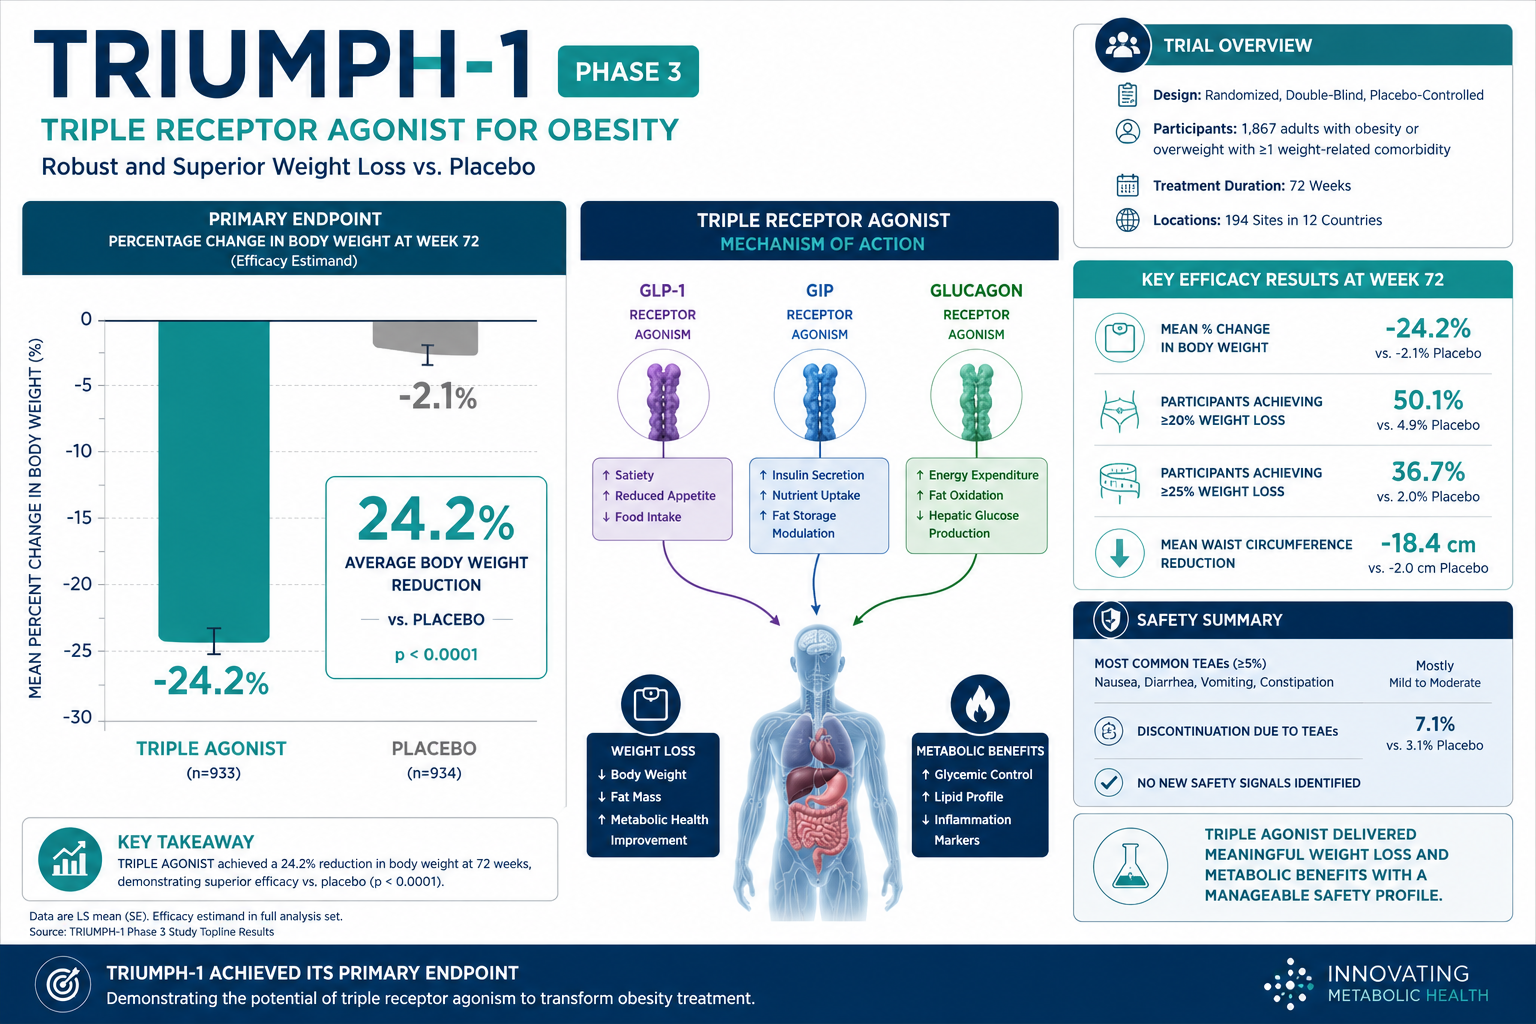
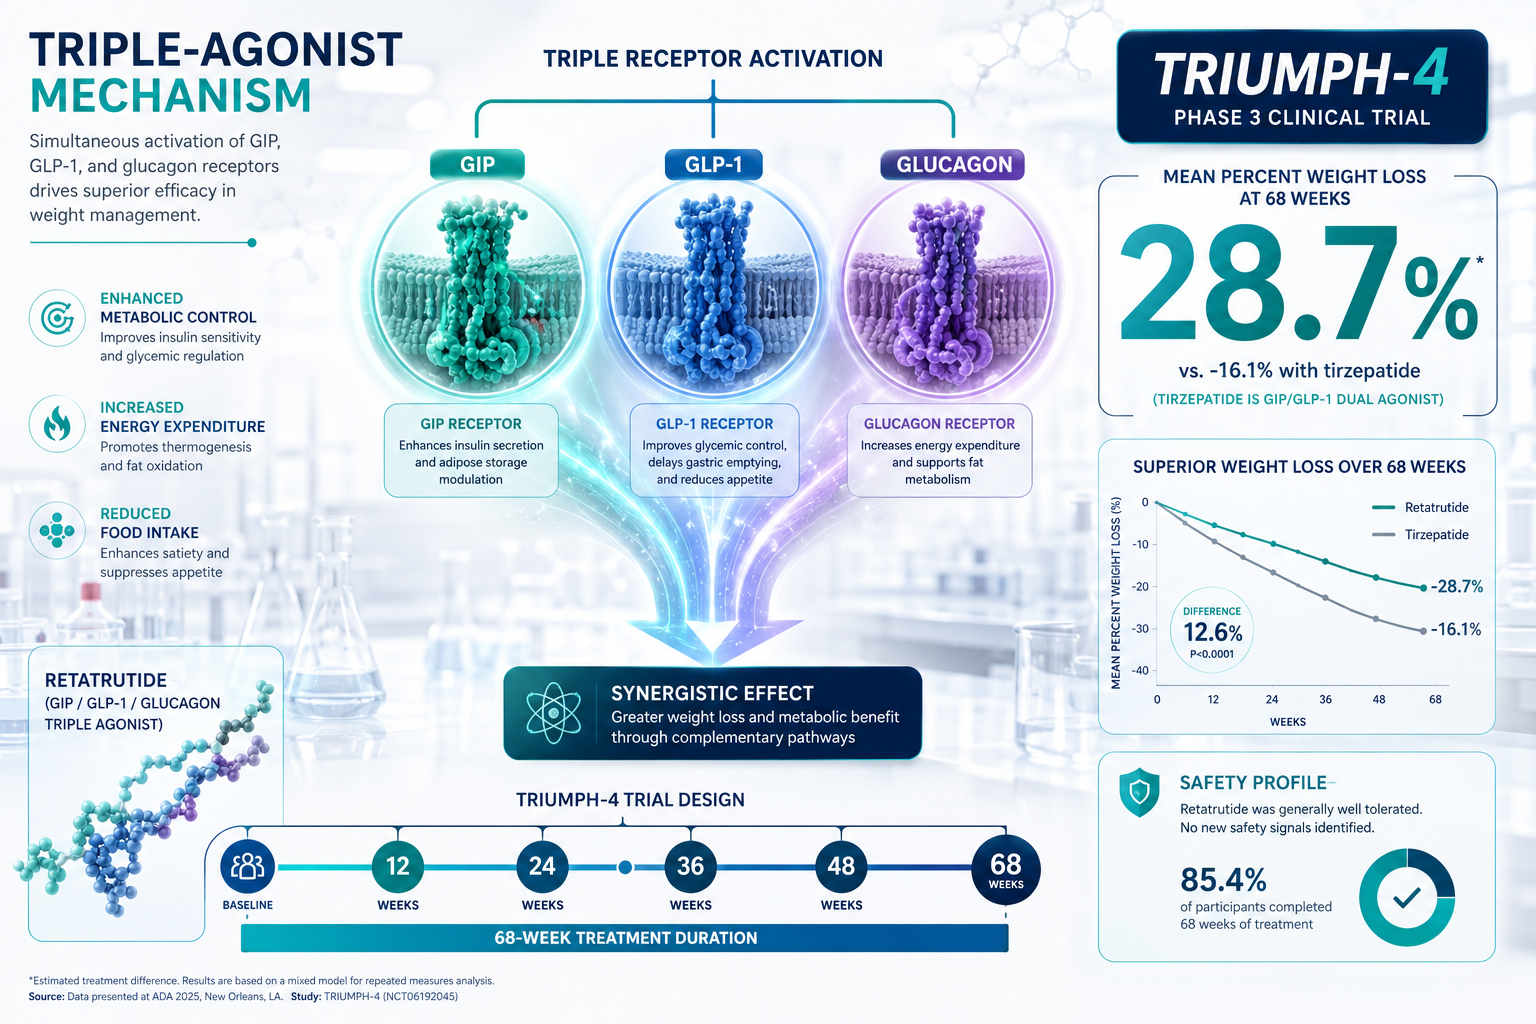
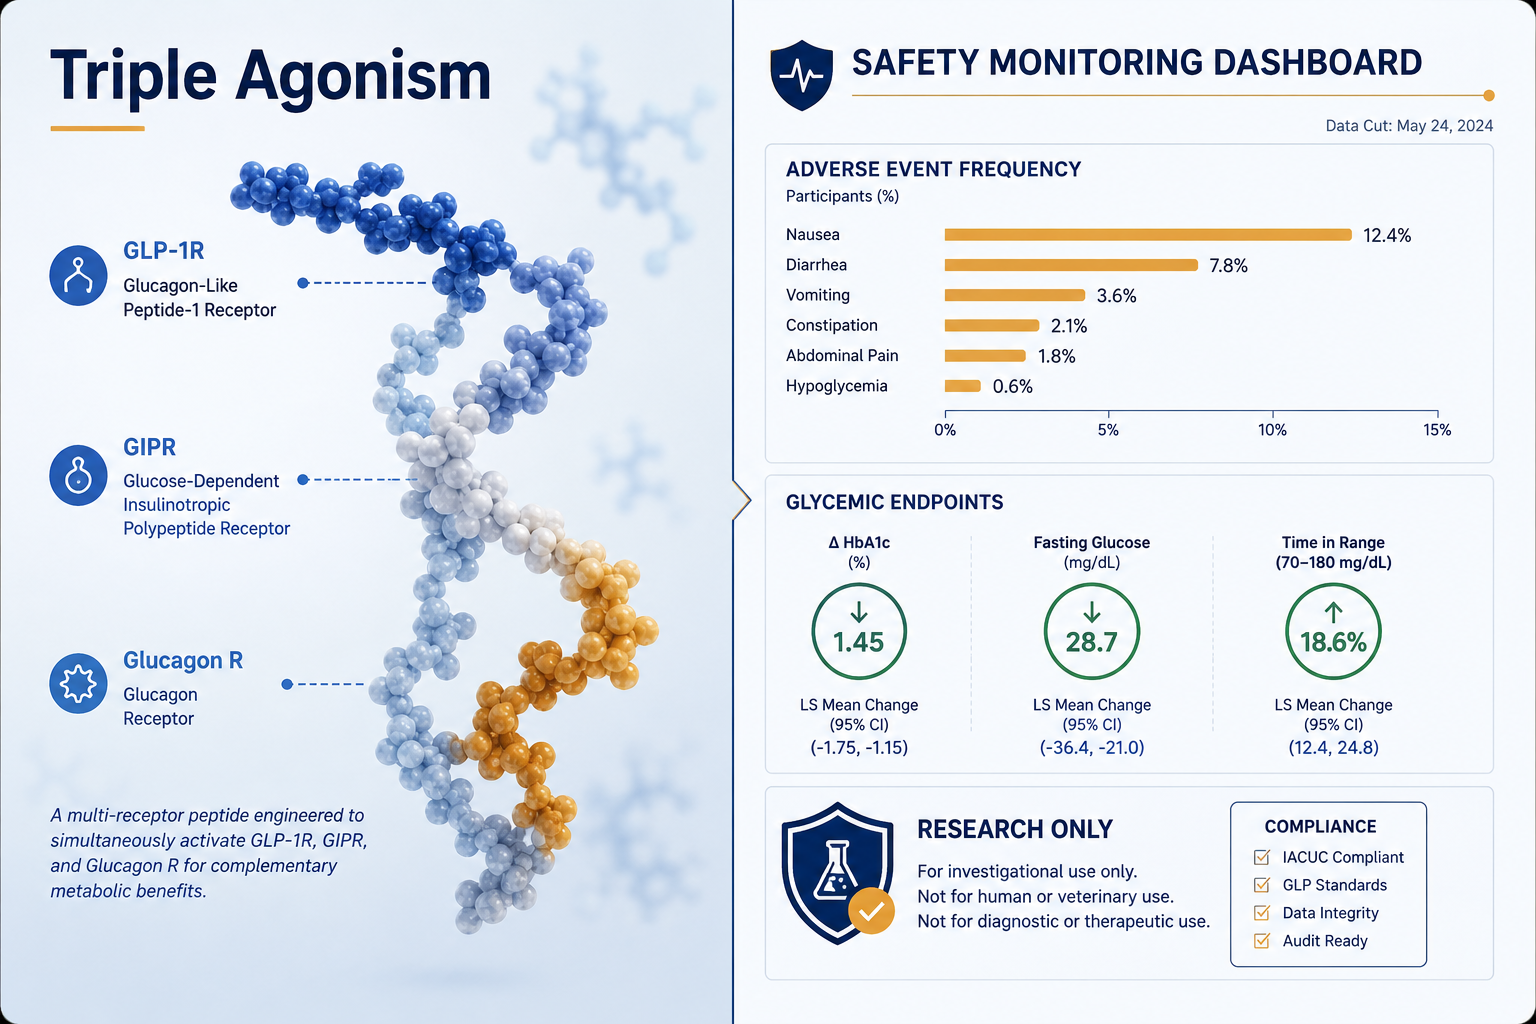
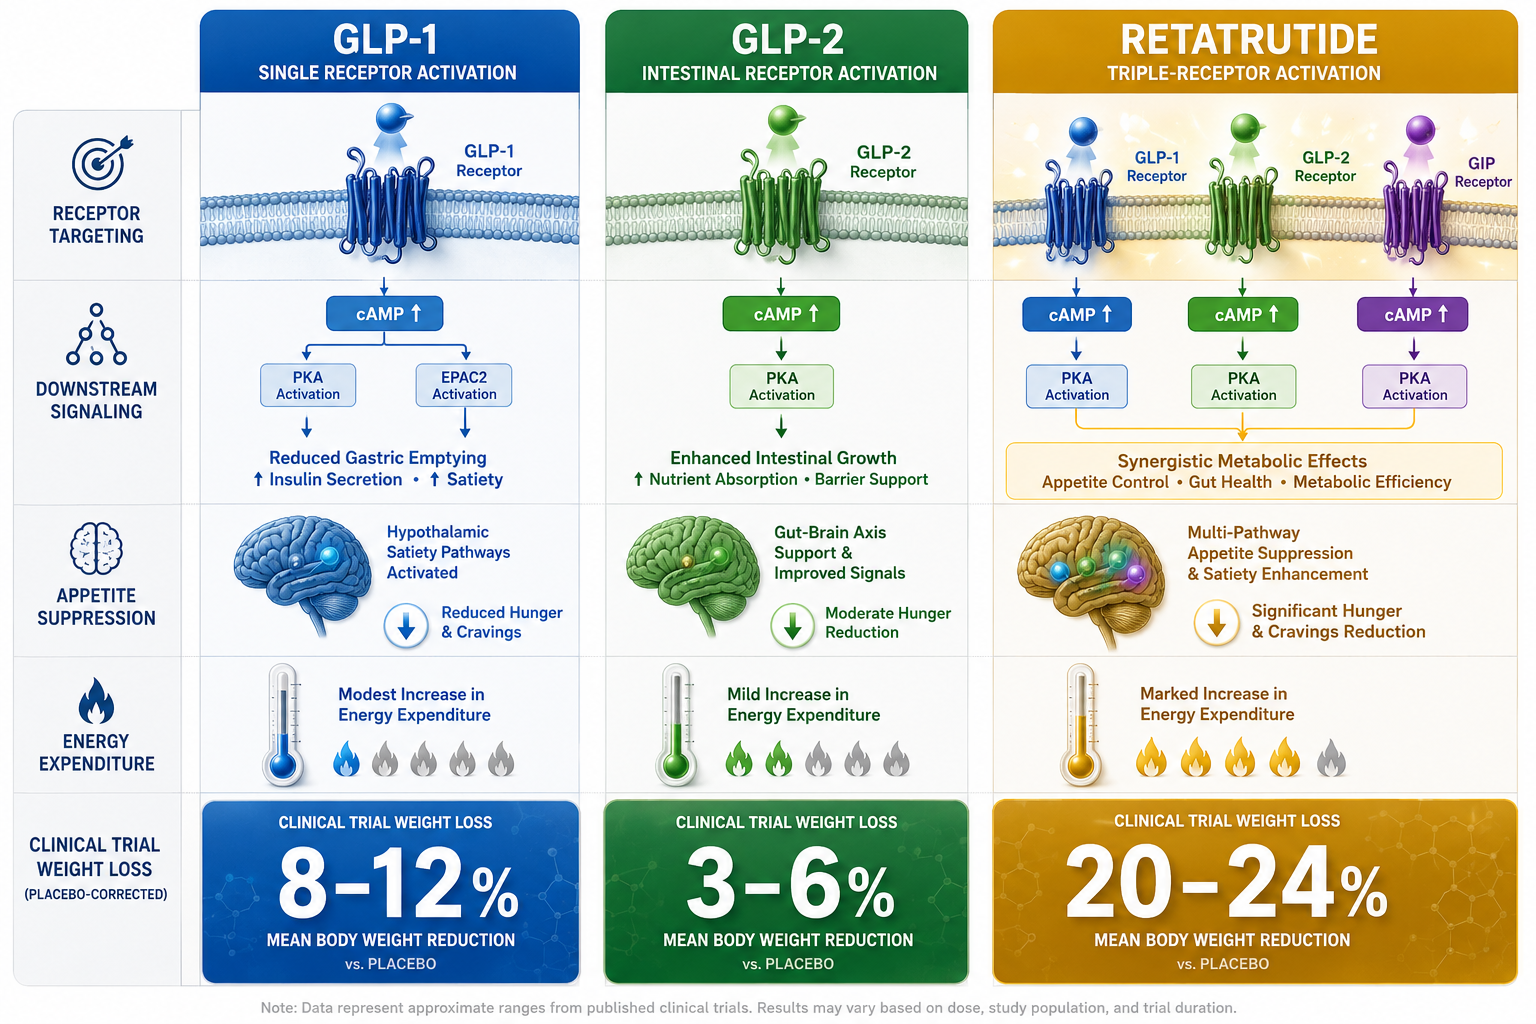
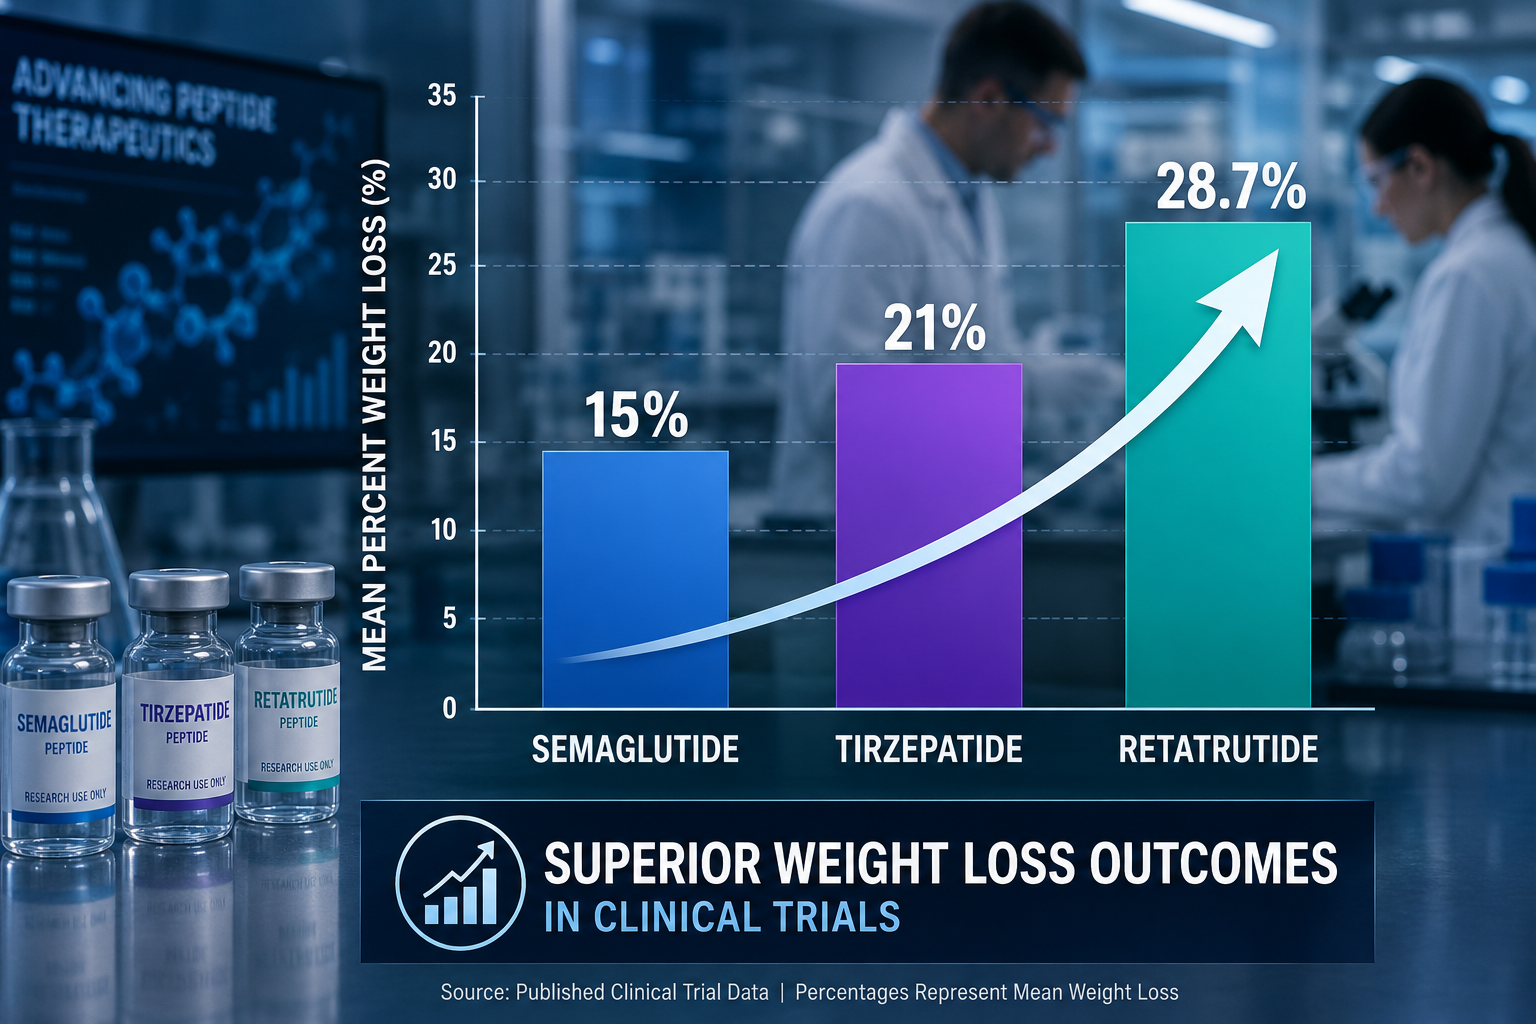
Retatrutide, developed under the designation LY3437943, is a single-molecule triple agonist that simultaneously activates glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon receptors. This multi-receptor engagement drives impressive reductions in body weight and improvements in metabolic markers, but it also amplifies the GI signaling cascades that produce nausea, vomiting, and early satiety.
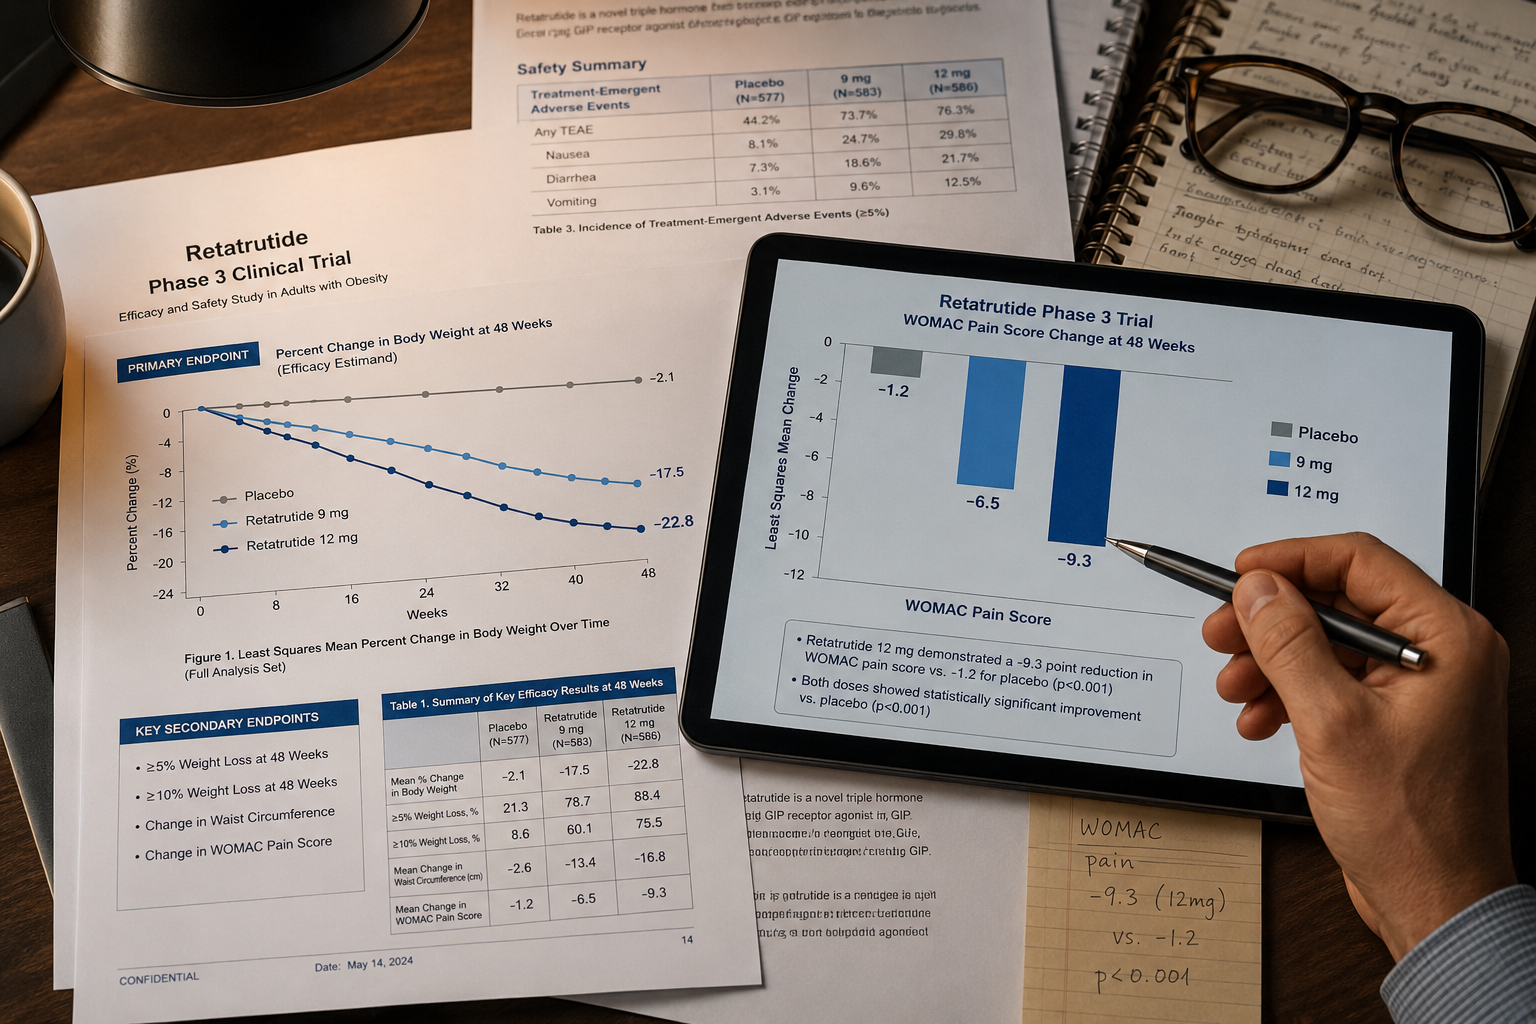
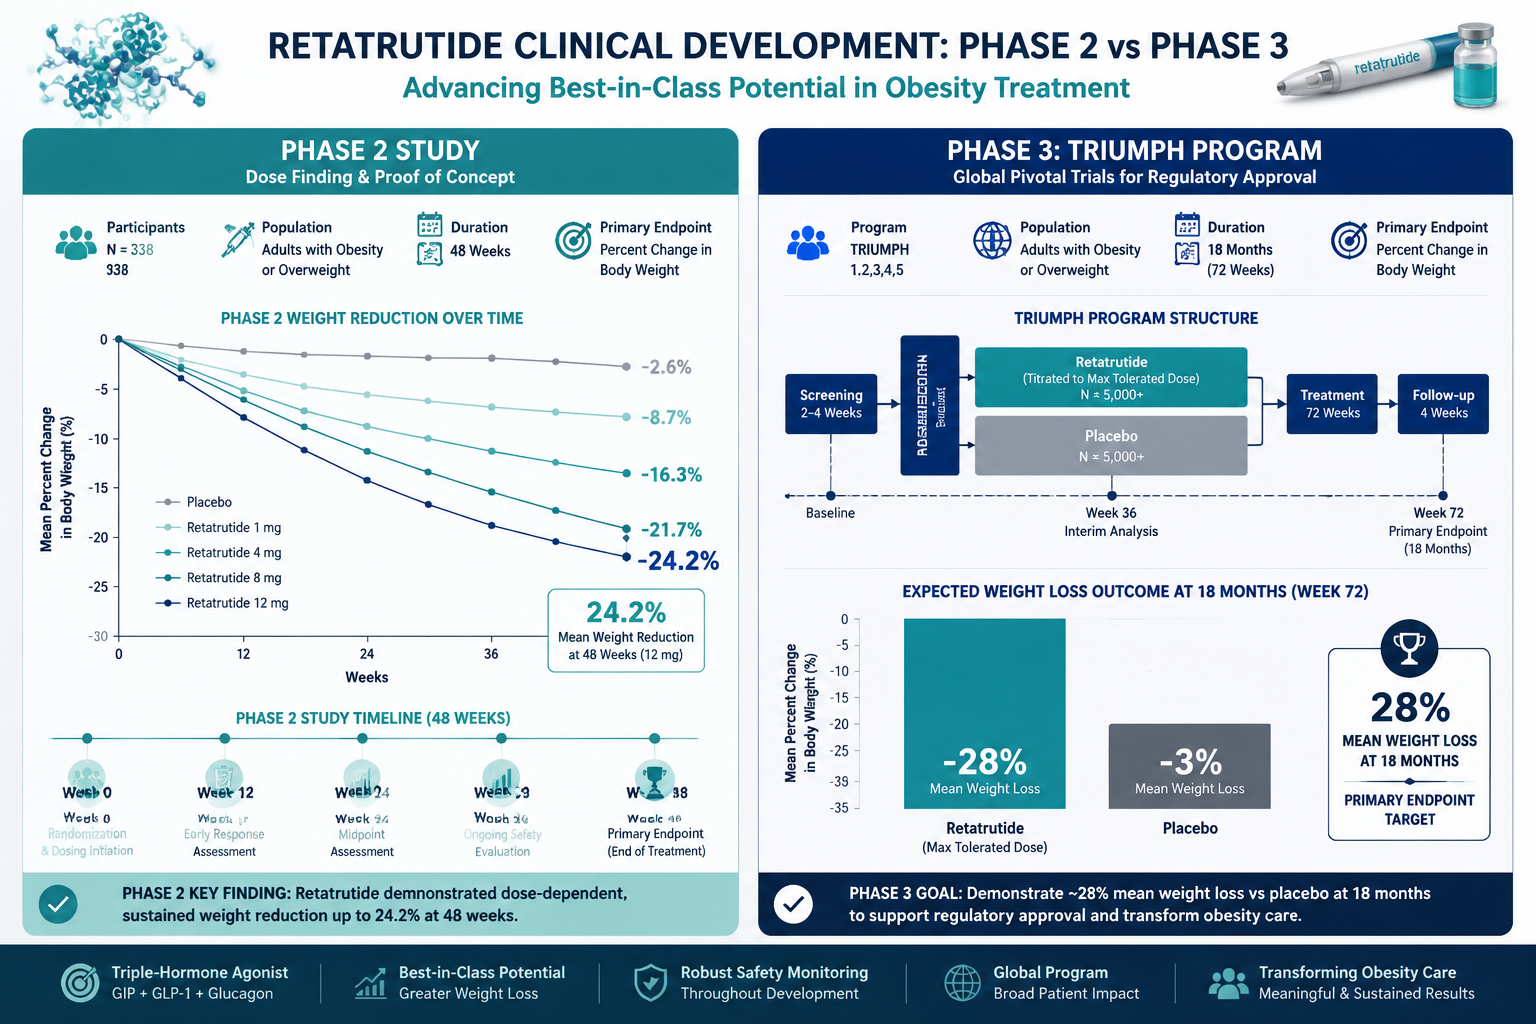
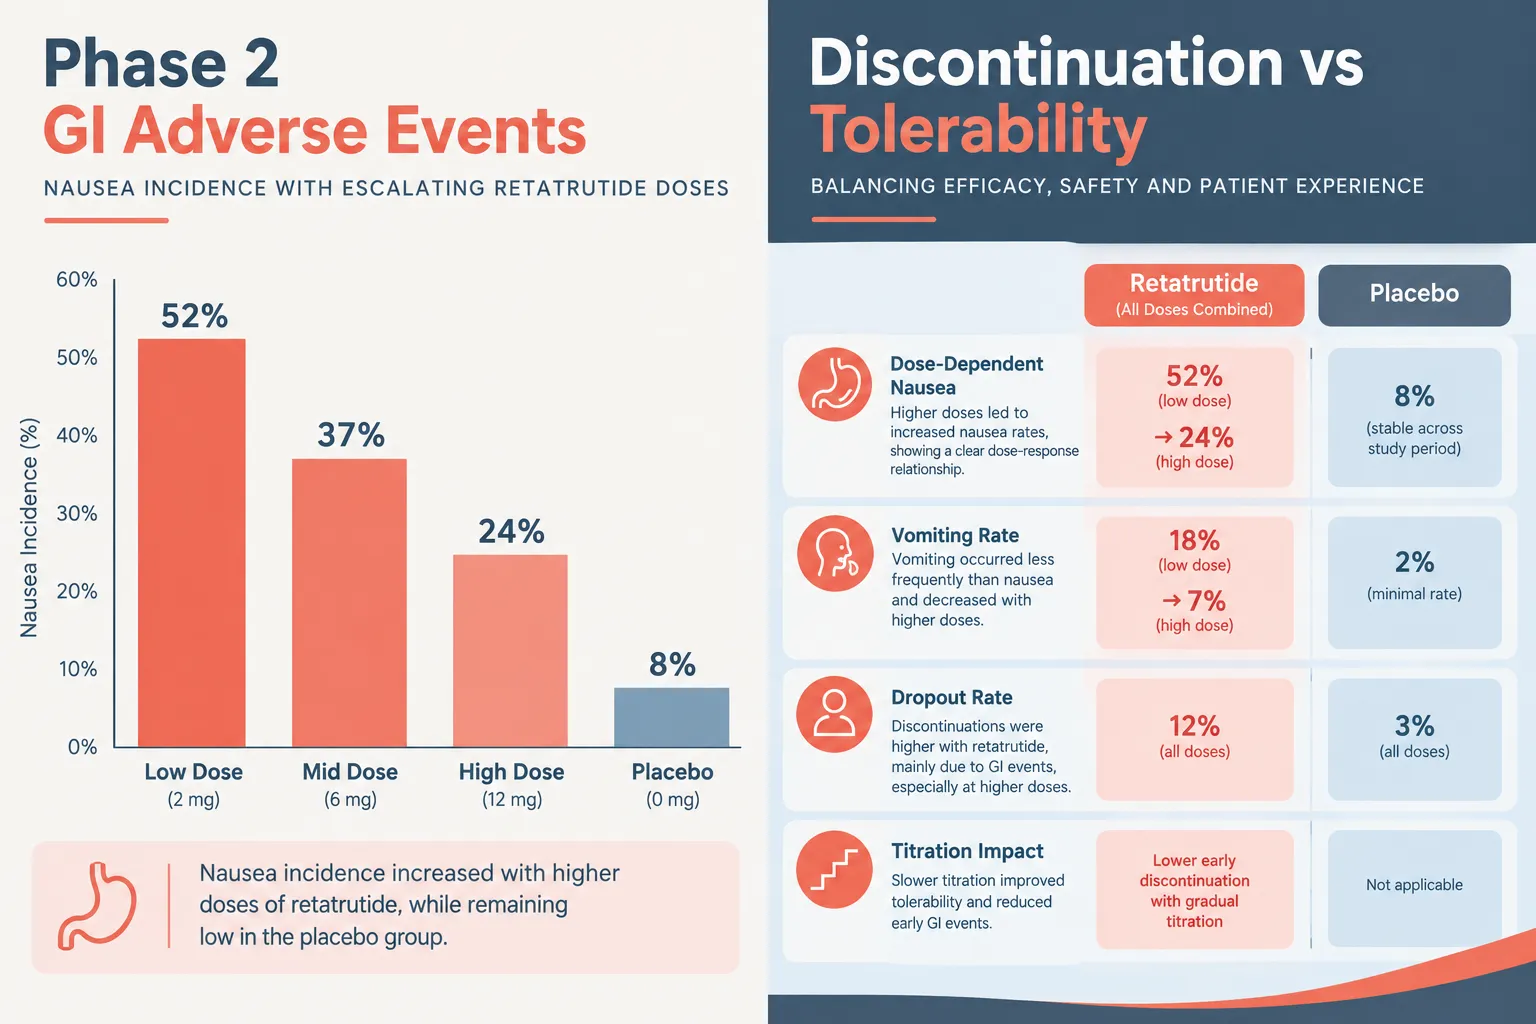
In Phase 2 dose-ranging studies, nausea incidence climbed steeply with dose escalation. At the highest tested doses, nausea was reported in over 40% of participants, with vomiting affecting a substantial subset. These figures exceed rates typically seen with GLP-1 receptor agonists alone, reflecting the additive GI burden of triple incretin engagement. Researchers exploring retatrutide clinical trials have consistently flagged GI tolerability as the primary dose-limiting factor.
The timing of adverse events follows a predictable pattern: symptoms peak during dose escalation phases and tend to attenuate as participants acclimate. However, the severity during escalation is sufficient to drive meaningful discontinuation rates, which in turn compromises the statistical integrity of long-term efficacy data.
Key GI adverse event characteristics in retatrutide research:
| Adverse Event | Onset Timing | Dose Relationship | Primary Mechanism |
|---|---|---|---|
| Nausea | Early escalation | Dose-dependent | GLP-1 vagal activation, 5-HT3 signaling |
| Vomiting | Concurrent with nausea | Dose-dependent | Central emetic pathway activation |
| Early satiety | Persistent | Moderate | Gastric motility slowing |
| Discontinuation | Peak escalation | High-dose cohorts | Cumulative GI burden |
The 5-HT3 Pathway: Why Ondansetron Is Relevant
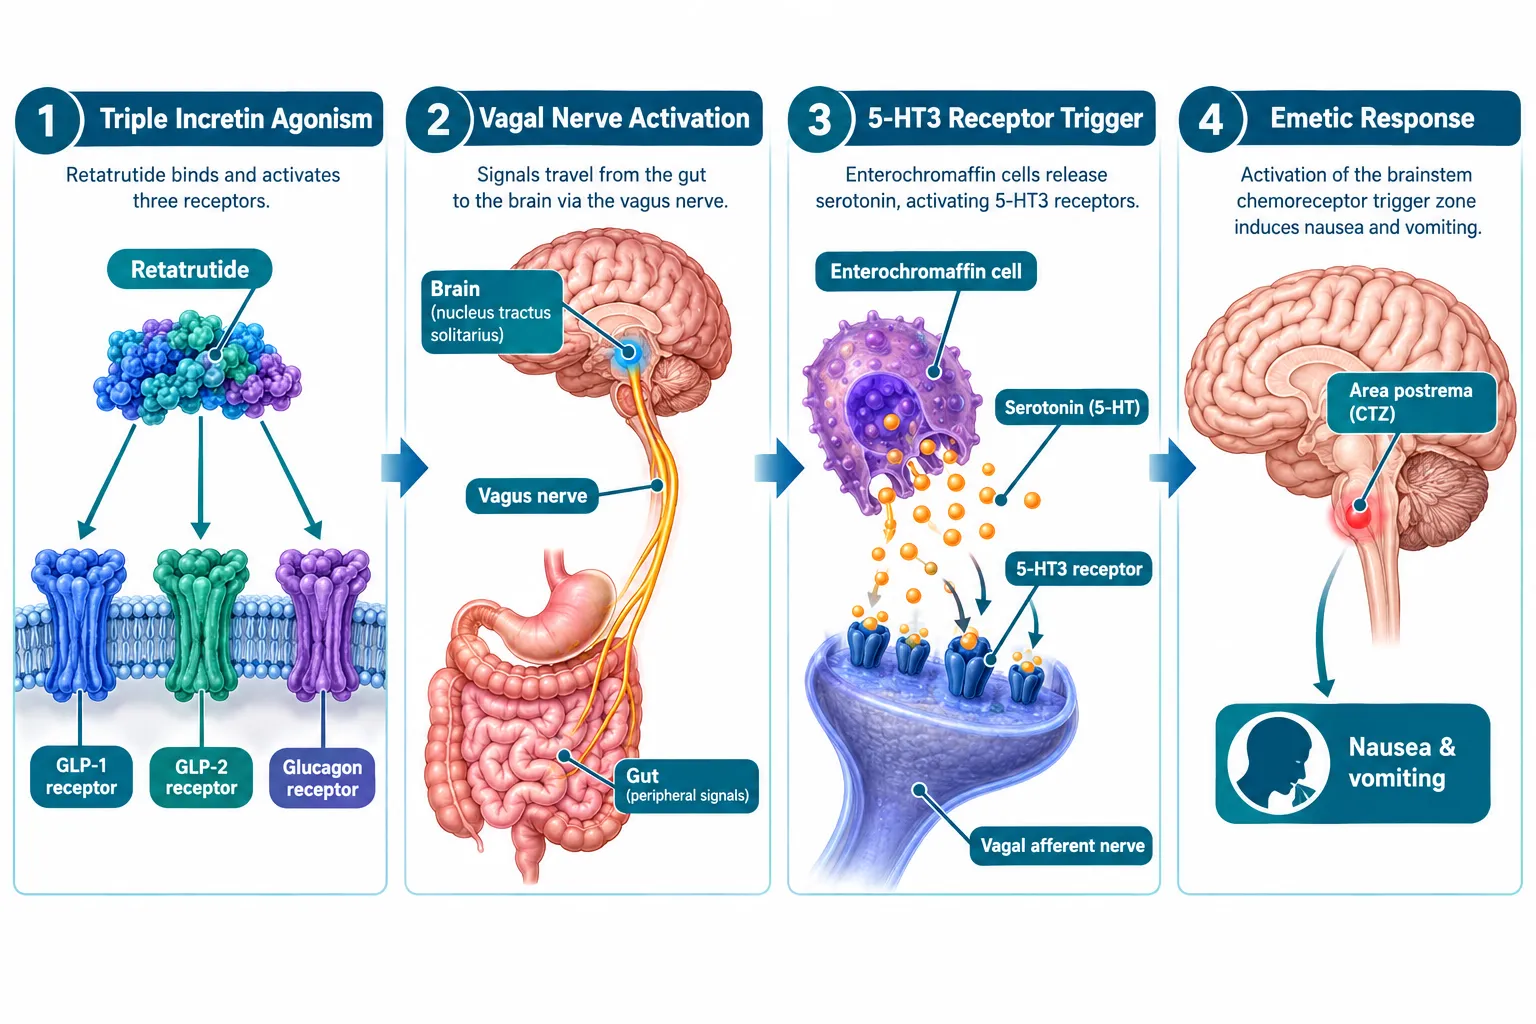
The central question in evaluating antiemetic protocols in incretin research involving ondansetron mechanisms during GLP-3 retatrutide administration lies in the biology of serotonin signaling. GLP-1 receptor activation in the gut stimulates enterochromaffin cells to release serotonin (5-hydroxytryptamine, or 5-HT). This serotonin binds to 5-HT3 receptors on vagal afferent neurons, transmitting an emetic signal to the brainstem's chemoreceptor trigger zone (CTZ) and the nucleus tractus solitarius (NTS).
Ondansetron is a highly selective 5-HT3 receptor antagonist. By blocking these receptors at both peripheral (gut-vagal) and central (CTZ) sites, it interrupts the serotonin-mediated emetic cascade before it reaches full activation. This dual-site mechanism makes it mechanistically well-suited to incretin-induced nausea, which originates peripherally but is amplified centrally.
Ondansetron's selectivity for the 5-HT3 receptor makes it a pharmacologically logical candidate for managing the serotonin-driven nausea associated with potent multi-incretin agonists like retatrutide.
The triple-agonist profile of retatrutide likely intensifies this cascade compared to single-receptor agents. Glucagon receptor activation adds motility effects, while GIP receptor engagement may further modulate gut hormone signaling. The cumulative result is a more complex emetic environment than ondansetron was originally designed to address, but one in which 5-HT3 blockade still targets a primary mechanistic node.
Current Protocol Gaps and the Path Forward
Despite the clear mechanistic rationale, a critical evidence gap exists. As of 2026, no published retatrutide trial has incorporated a formal, pre-specified ondansetron antiemetic protocol. Current management strategies rely almost entirely on conservative dose titration schedules and general supportive care guidance. Participants are typically advised to eat smaller meals, avoid high-fat foods, and wait out the escalation period.
This approach has limitations. Dose titration slows the research timeline and may prevent some participants from reaching target doses. Supportive care guidance is inconsistently applied across sites. And without standardized antiemetic co-administration data, researchers cannot determine whether pharmacological intervention would meaningfully reduce discontinuation rates.
For those sourcing research-grade compounds, the GLP-3 Reta 10mg research peptide represents one avenue for preclinical investigation, and resources on buying GLP-3 Reta for research purposes are available for qualified investigators. Similarly, researchers exploring related peptide tolerability profiles may find value in SS-31 mitochondrial research themes as a parallel framework for understanding cellular stress responses during peptide administration.
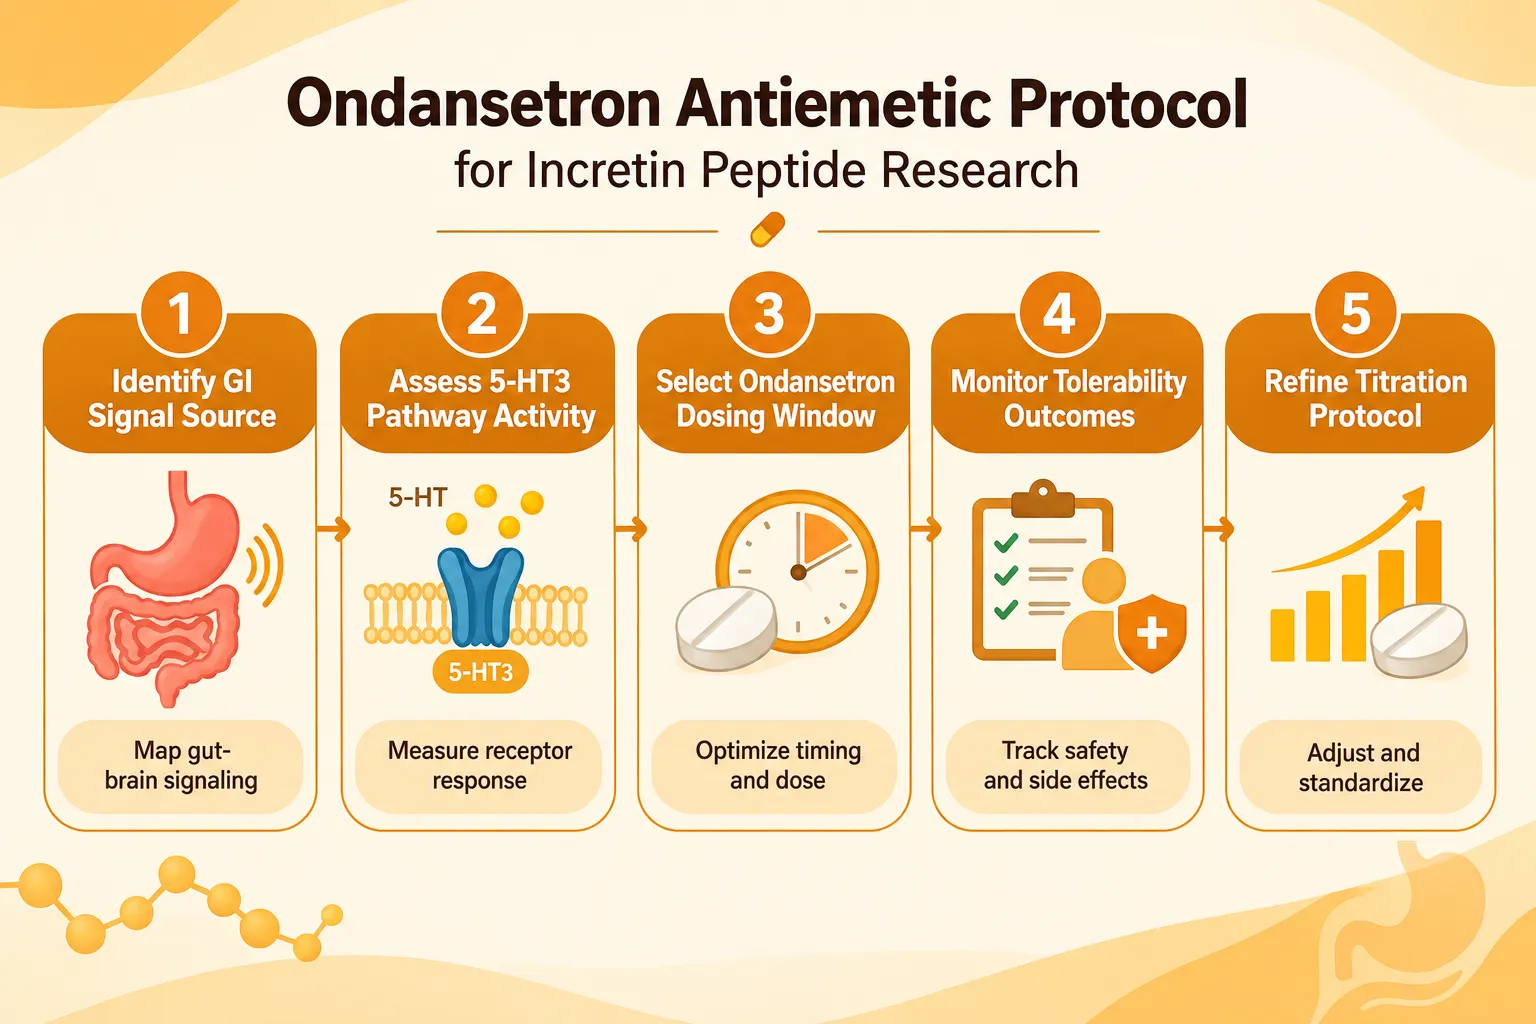
Proposed elements of a structured ondansetron protocol for incretin research:
- Timing: Administer ondansetron 30-60 minutes prior to retatrutide injection during dose escalation phases.
- Dosing window: Standard antiemetic dosing (4-8 mg oral) aligned with escalation schedules.
- Duration: Protocol-defined use limited to escalation periods, with reassessment at maintenance doses.
- Outcome tracking: Standardized nausea severity scales (e.g., FLIE, VAS) recorded at consistent intervals.
- Discontinuation monitoring: Compare dropout rates between antiemetic-supported and standard-care arms.
Researchers interested in buying retatrutide peptide for preclinical work should also consider how antiemetic co-administration variables will be documented in their protocols. Parallel work in Semax research demonstrates how neuropeptide tolerability frameworks can inform protocol design across compound classes.
The risk-benefit calculus here is straightforward: if ondansetron reduces early discontinuation by even a modest percentage, the downstream gains in data completeness and statistical power justify its inclusion in trial designs. The question is no longer whether to study this intervention, but how to structure that study rigorously.
Conclusion
Evaluating antiemetic protocols in incretin research, specifically ondansetron mechanisms during GLP-3 retatrutide administration, is no longer a secondary concern. It is a prerequisite for generating reliable, high-quality data from one of the most promising metabolic research compounds in development.
Actionable next steps for research teams:
- Incorporate pre-specified 5-HT3 antagonist co-administration arms into upcoming retatrutide Phase 3 sub-studies.
- Standardize nausea outcome measurement tools across all sites to enable meaningful cross-trial comparison.
- Publish tolerability sub-analyses that isolate the effect of antiemetic support on dose completion rates.
- Engage regulatory bodies early on antiemetic co-administration as a protocol variable, not a post-hoc intervention.
The serotonin pathway is not a minor footnote in incretin pharmacology, it is a central driver of the GI burden that limits these compounds' research potential. Addressing it with the same rigor applied to efficacy endpoints will define the next generation of incretin trial design.