Enclomiphene and LH/FSH Pulsatility: A Sampling Design for Separating Endocrine Feedback From Circadian Variation
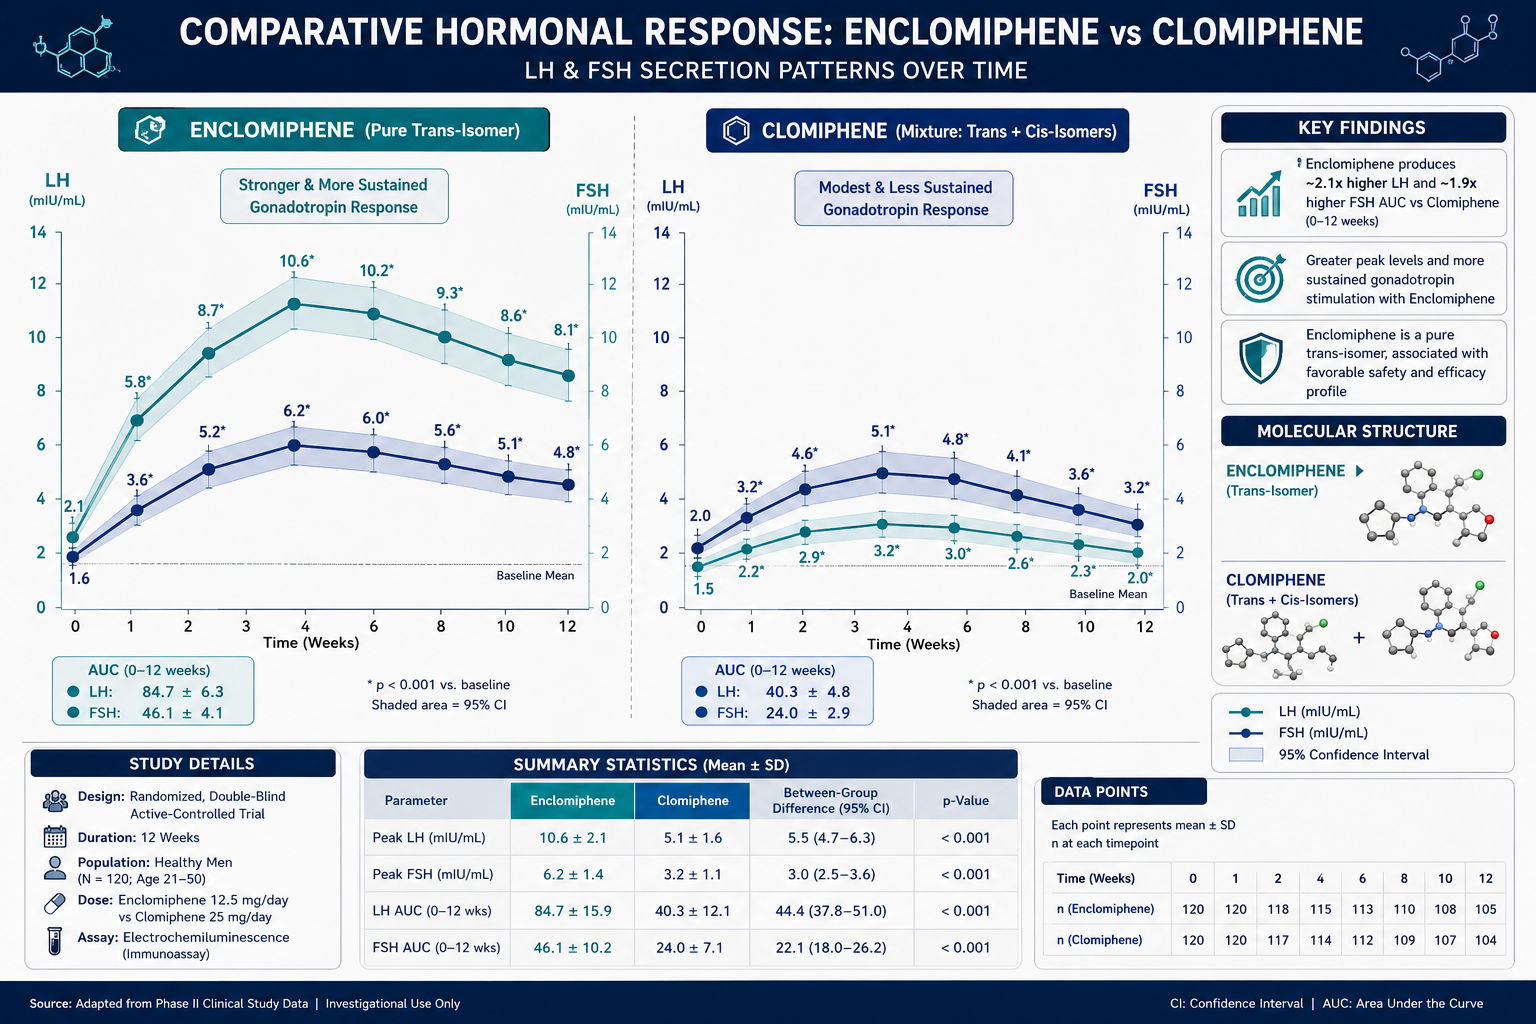
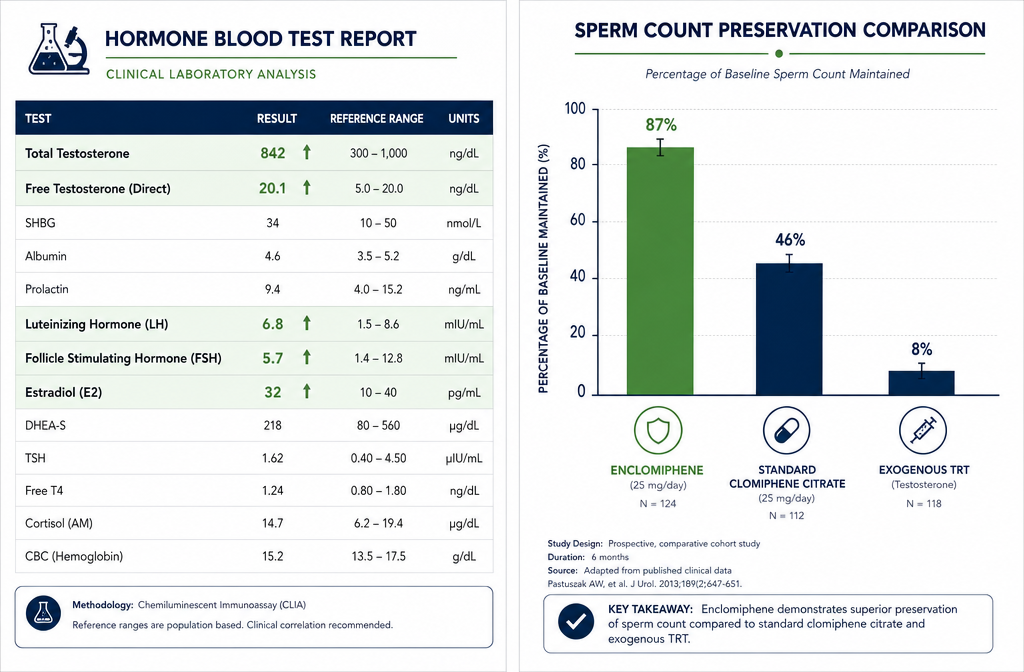
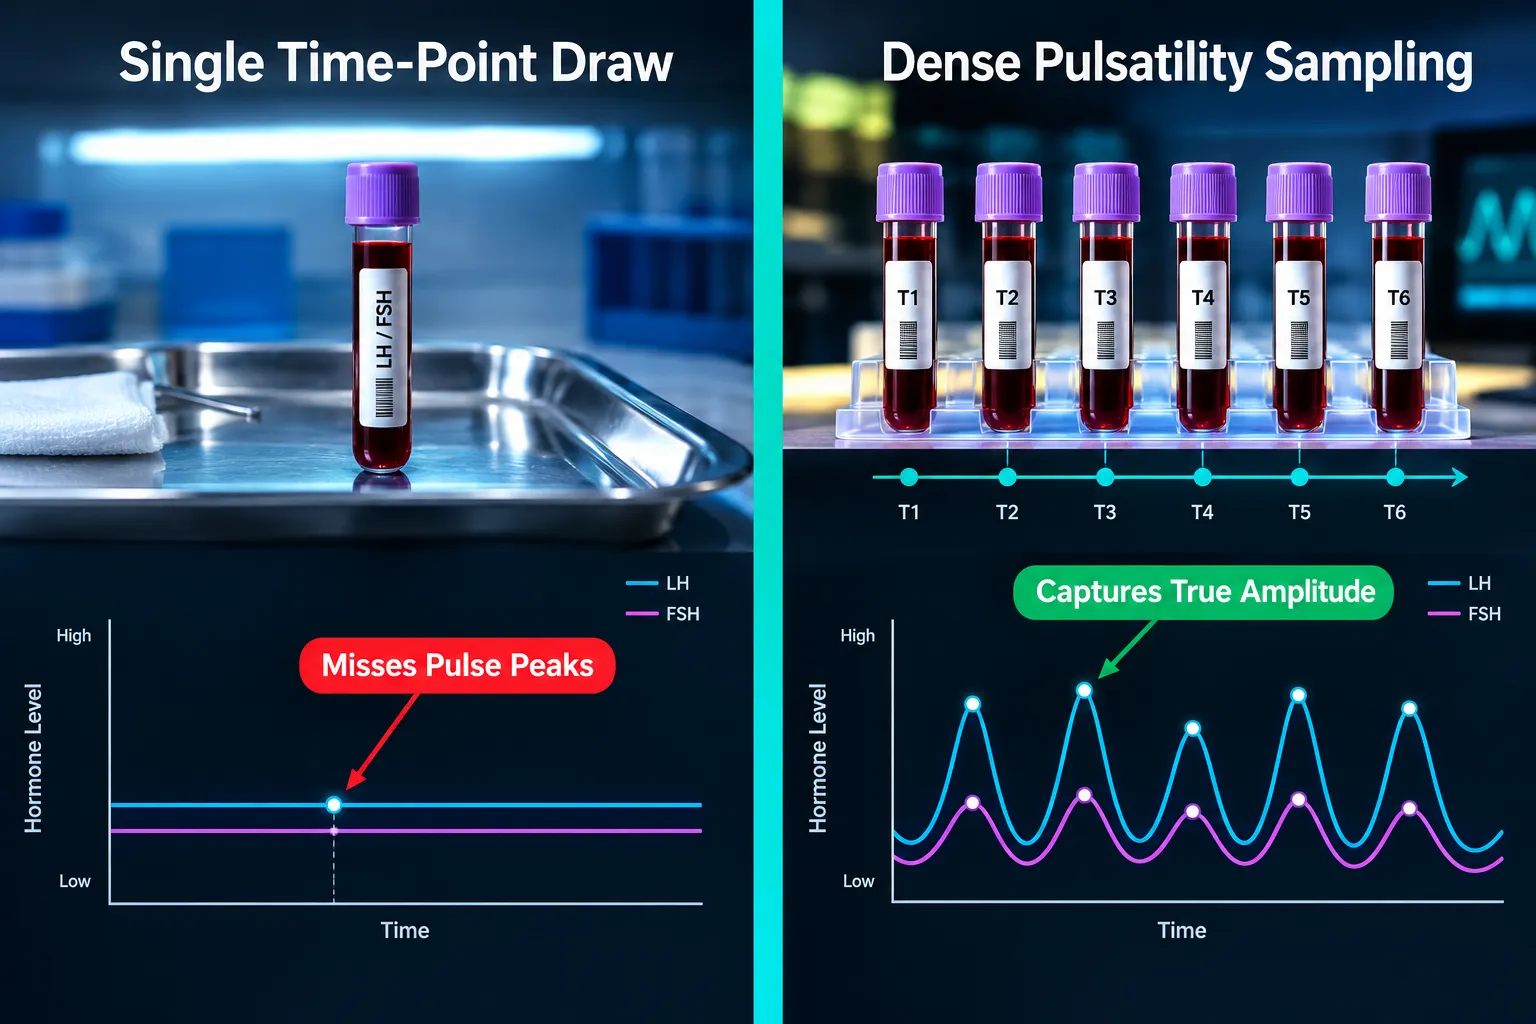
A single morning blood draw tells only a fraction of the story. When a 25 mg dose of enclomiphene pushed LH from 5.3 to 11.9 mIU/mL and FSH from 9.4 to 14.9 mIU/mL in one controlled trial, researchers noted something equally important: serum enclomiphene concentration peaks did not line up with LH secretion peaks. That mismatch is not a flaw in the drug, it is a warning about how endocrine data gets collected and interpreted.
Understanding enclomiphene and LH/FSH pulsatility: a sampling design for separating endocrine feedback from circadian variation requires thinking beyond single-point measurements and toward the temporal architecture of gonadotropin secretion.
Key Takeaways
- LH and FSH are released in discrete pulses, not steady streams, making single-timepoint draws unreliable.
- Enclomiphene's effect on gonadotropin levels can outlast its serum concentration peak, complicating sparse sampling.
- Capturing true pulsatility requires blood draws every 10 minutes over a 4-to-6-hour window.
- Circadian variation and estradiol-driven negative feedback both shape the LH/FSH signal independently.
- Dense, multi-day sampling schedules are the only validated way to separate drug effect from biological rhythm.
Why Pulsatile Secretion Makes Hormone Measurement Difficult
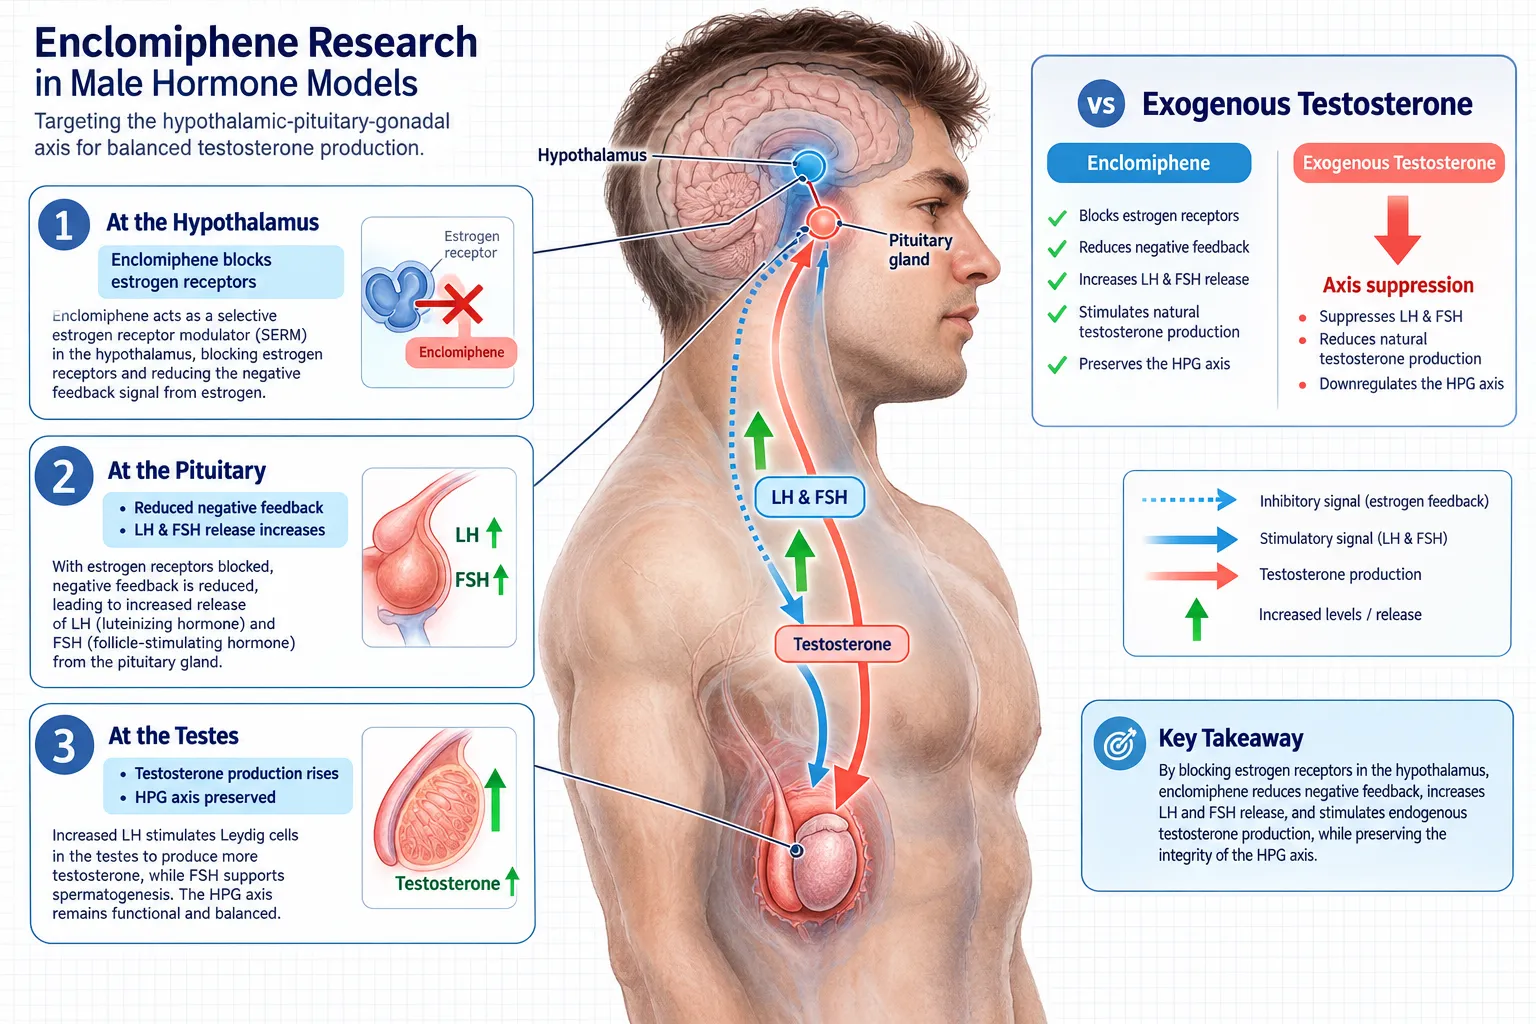
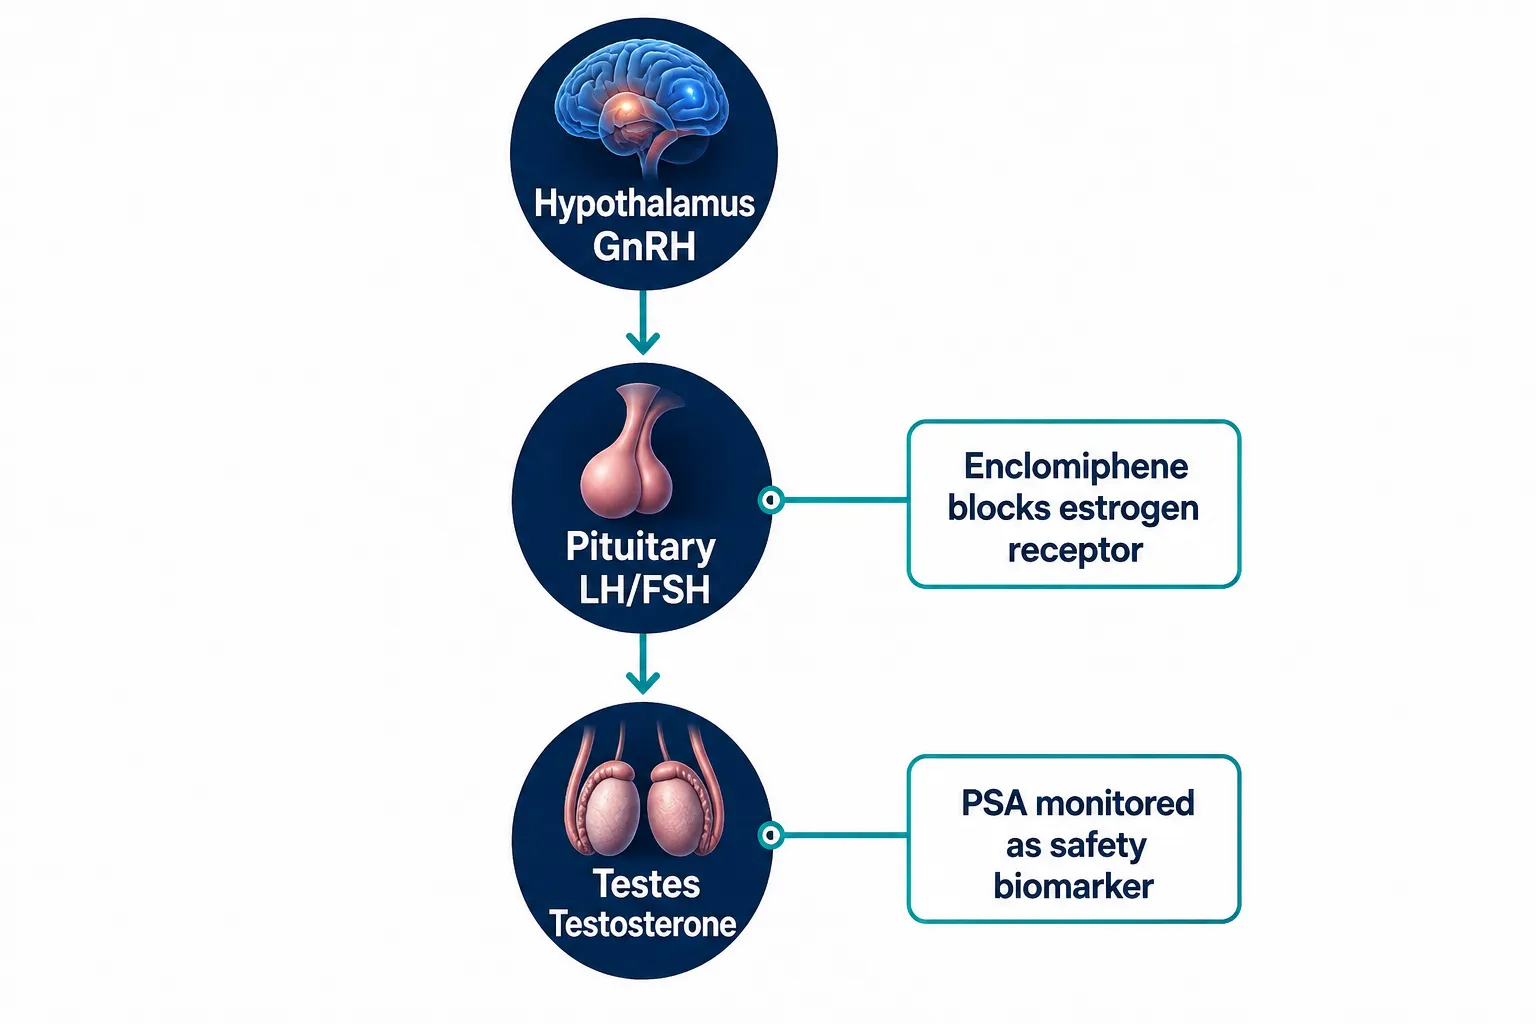
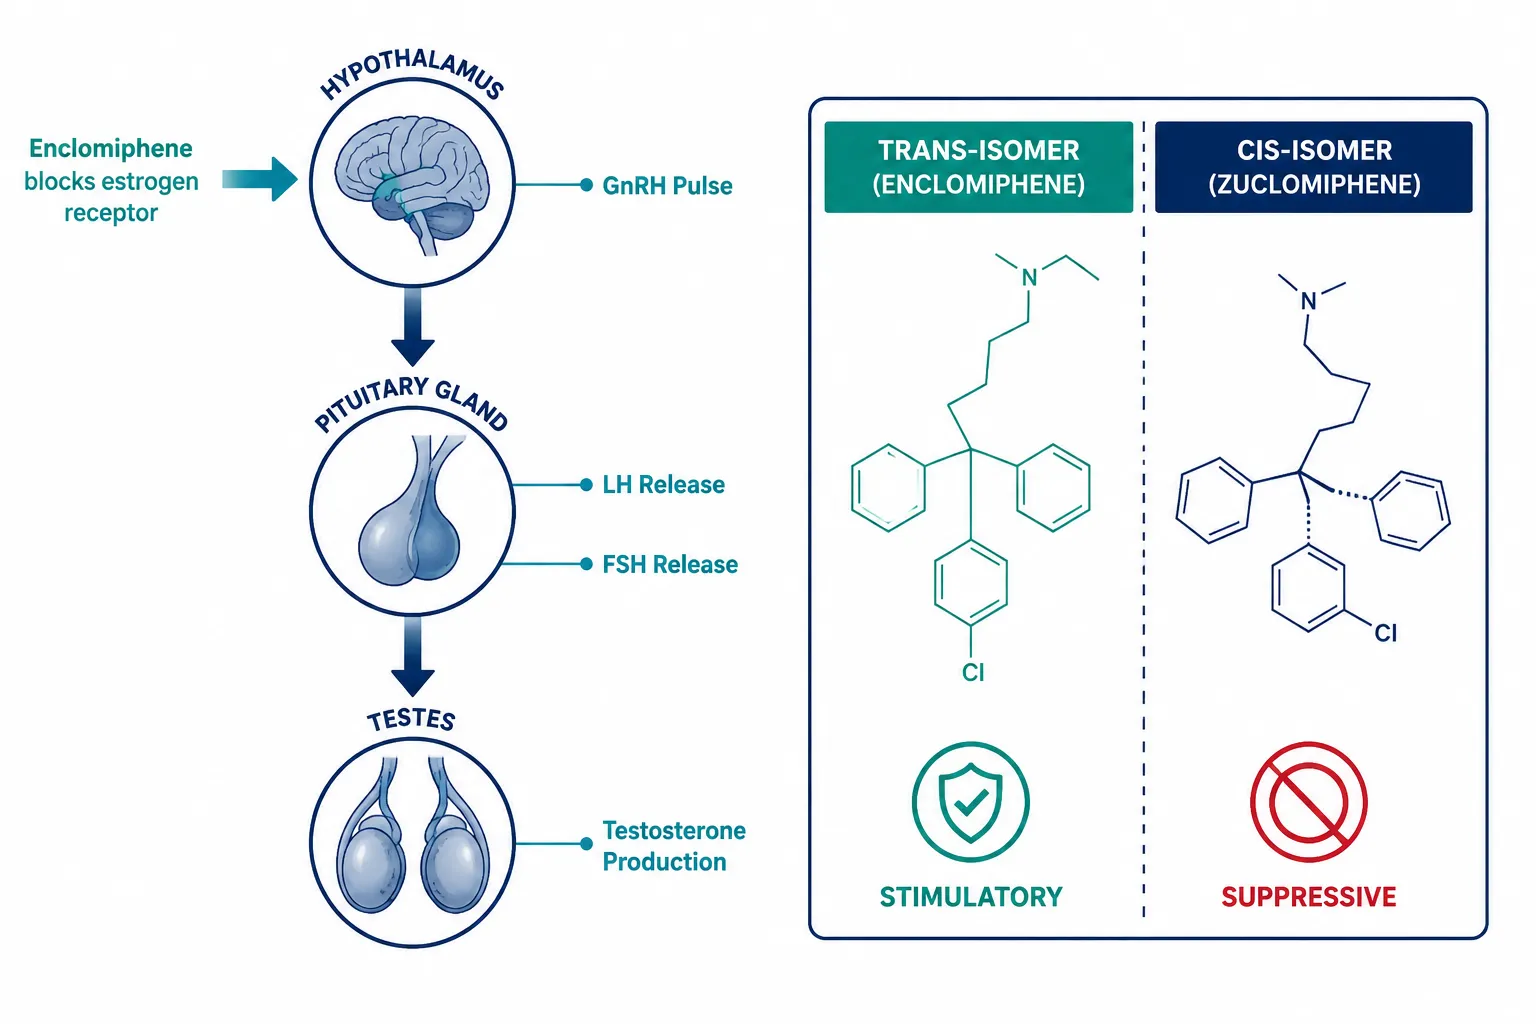
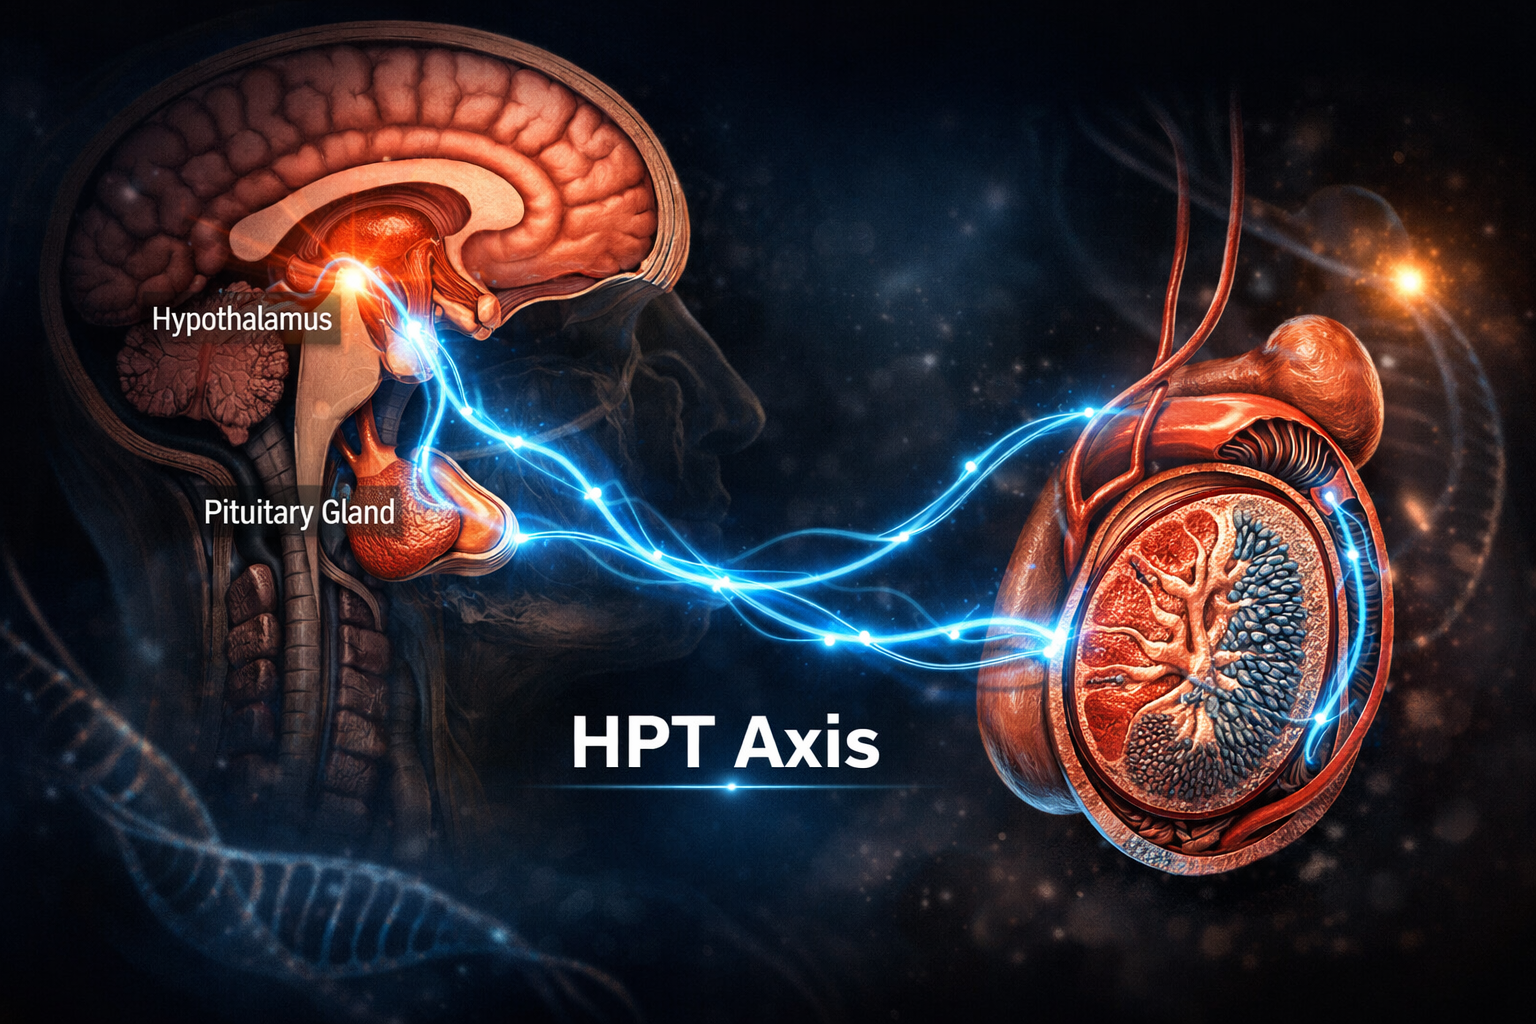
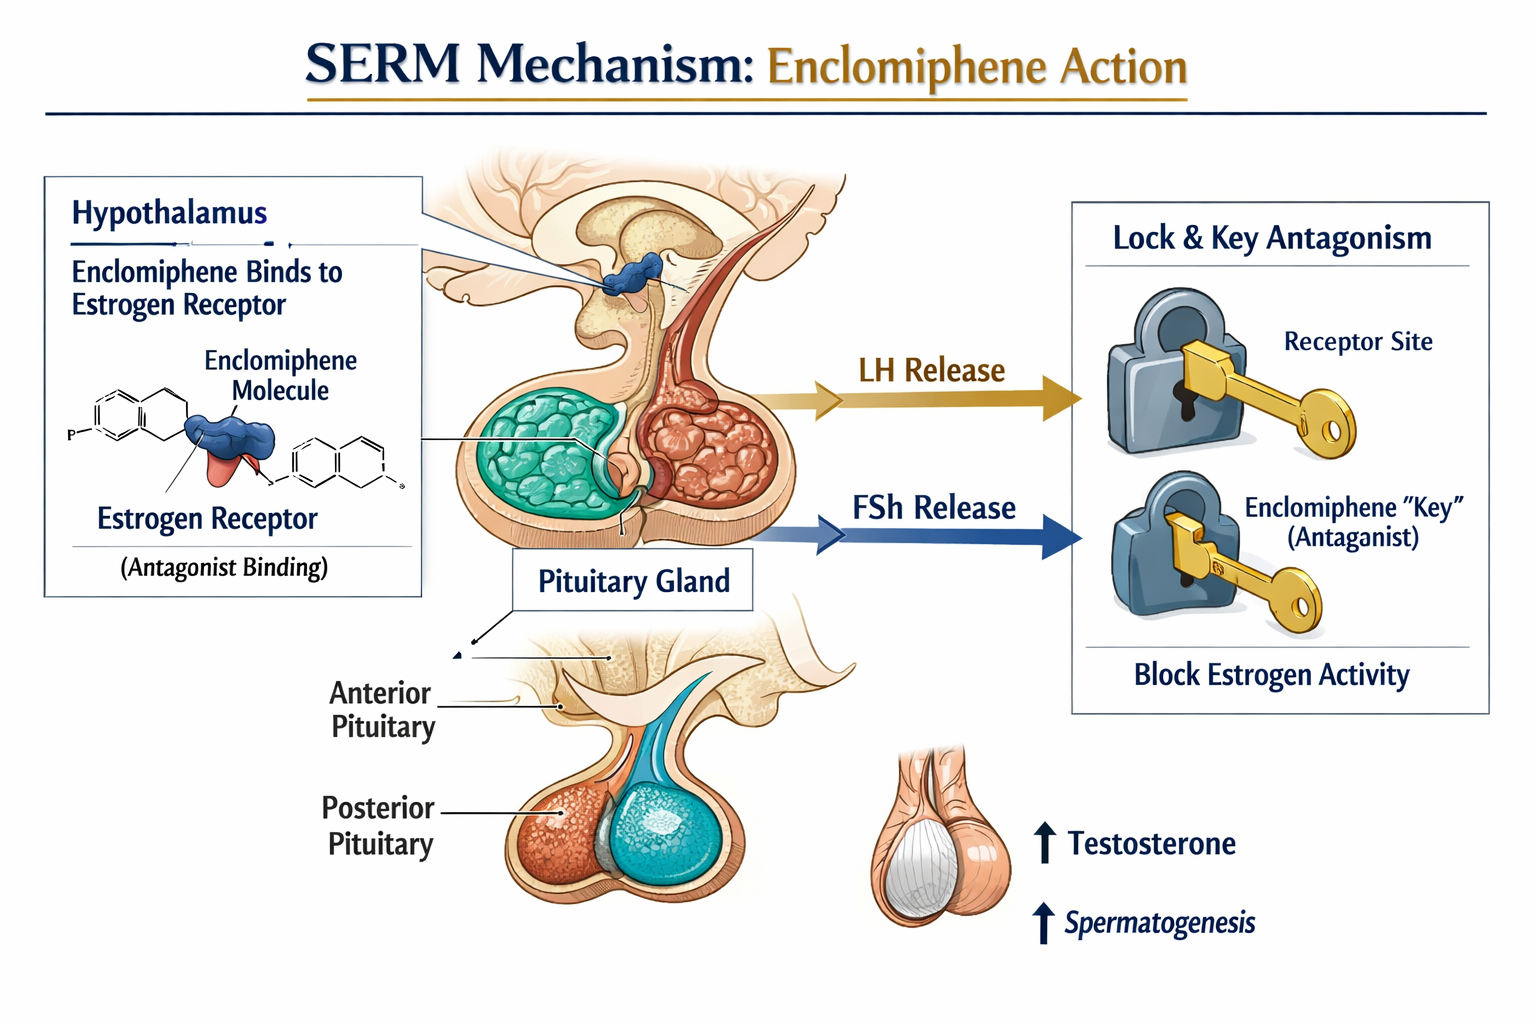
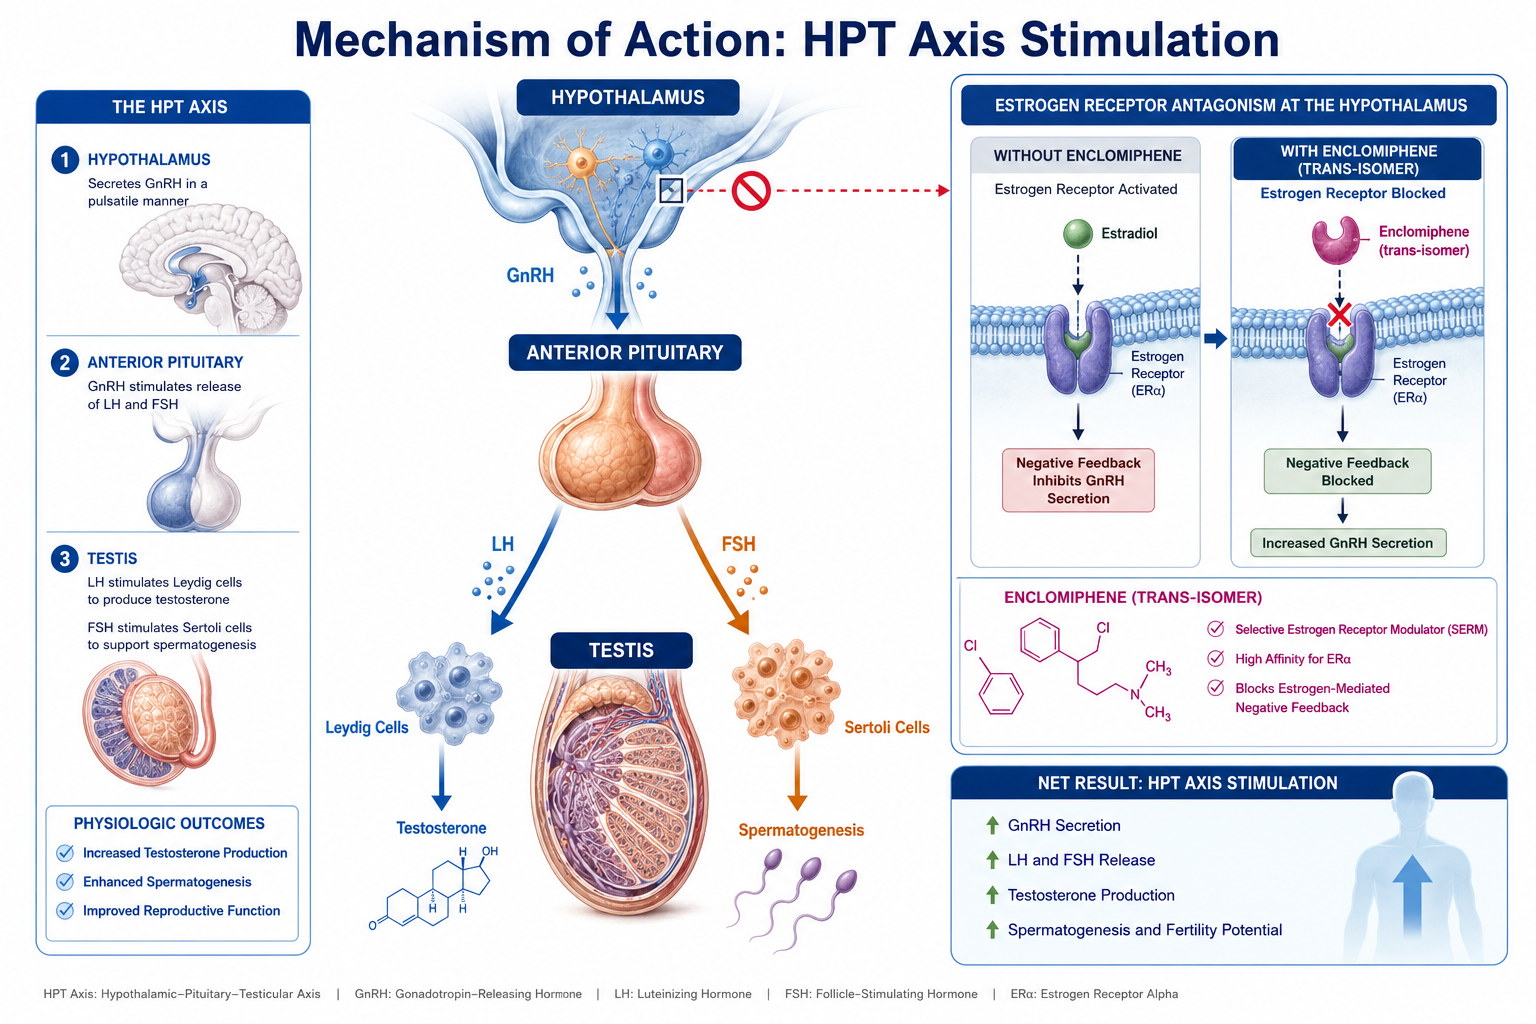
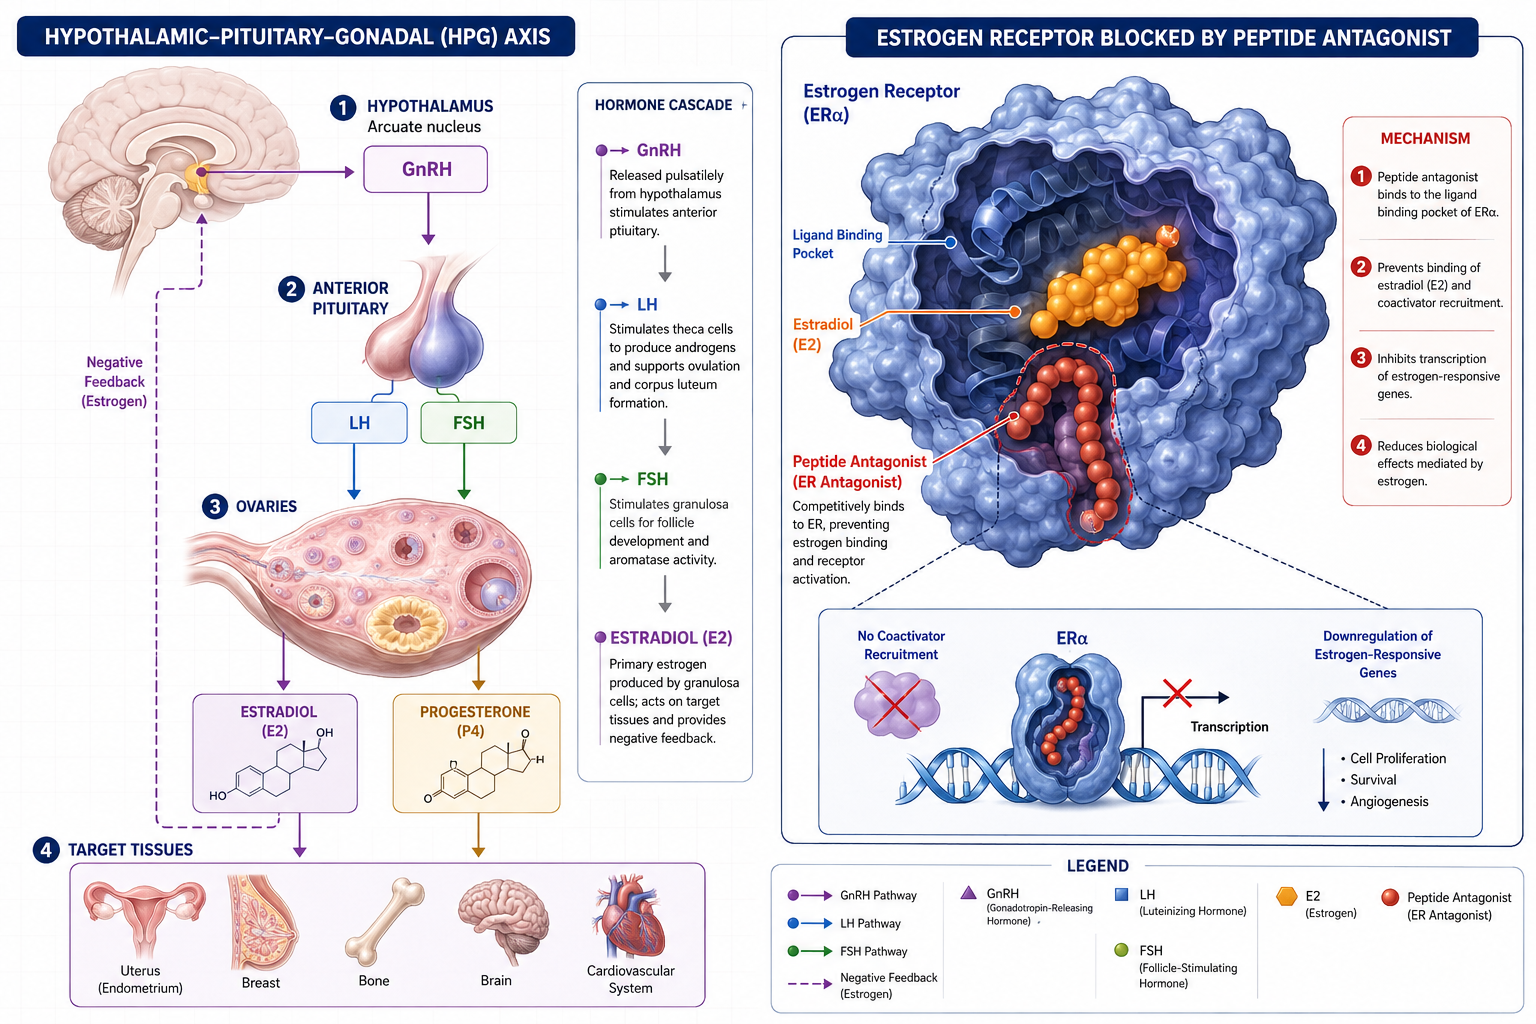
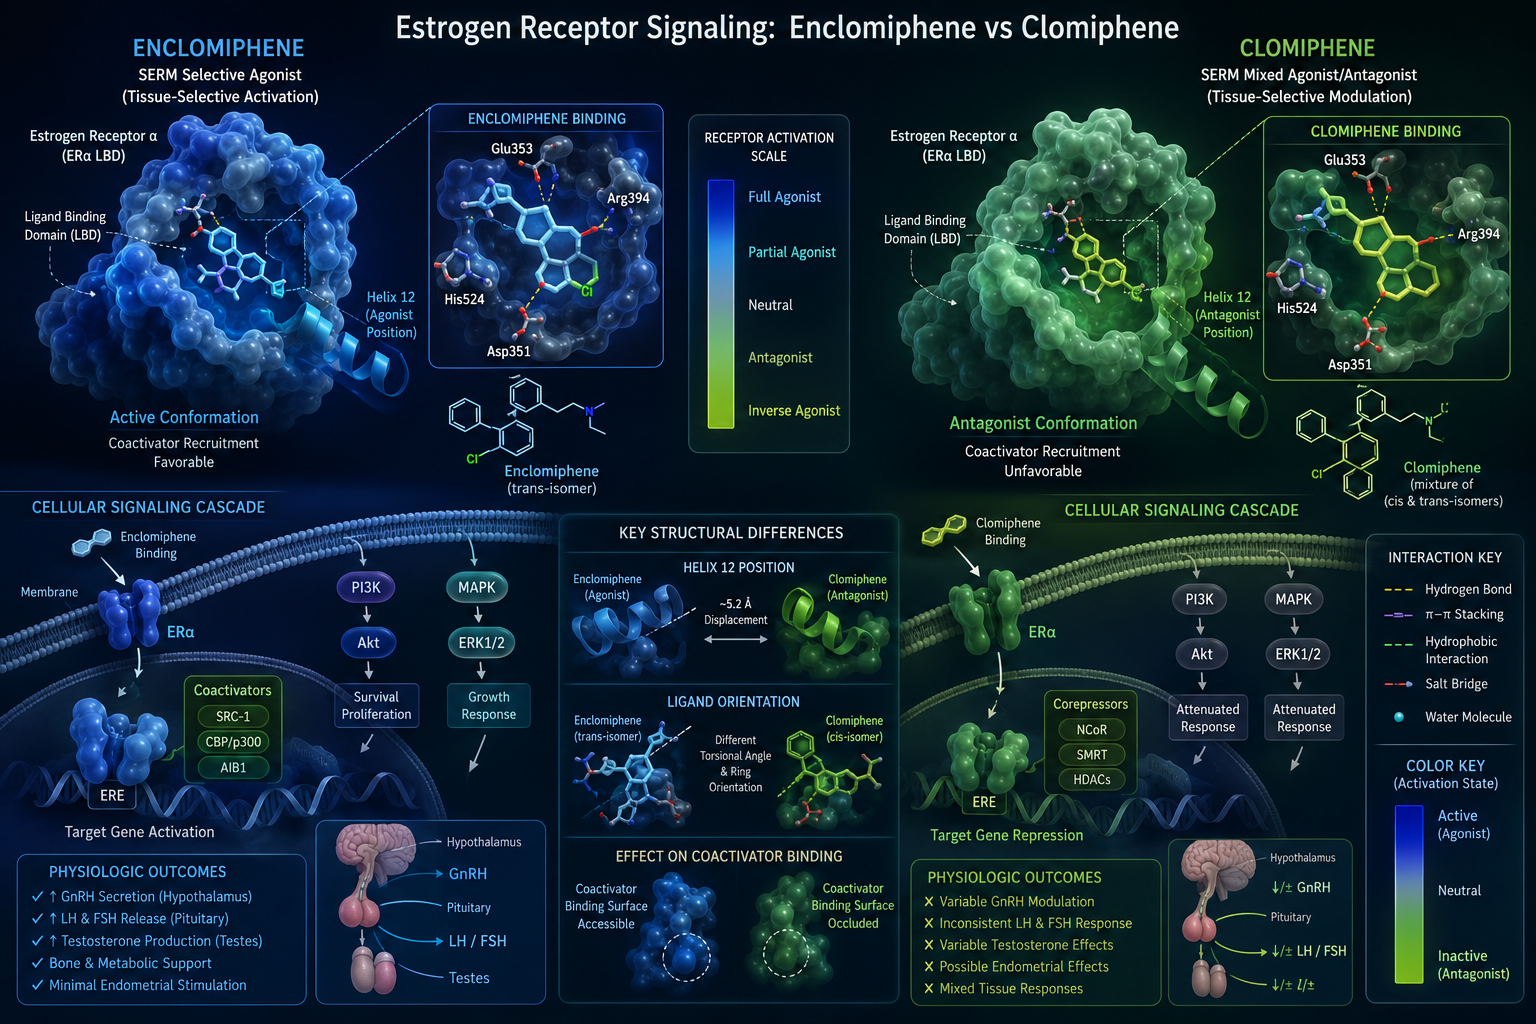
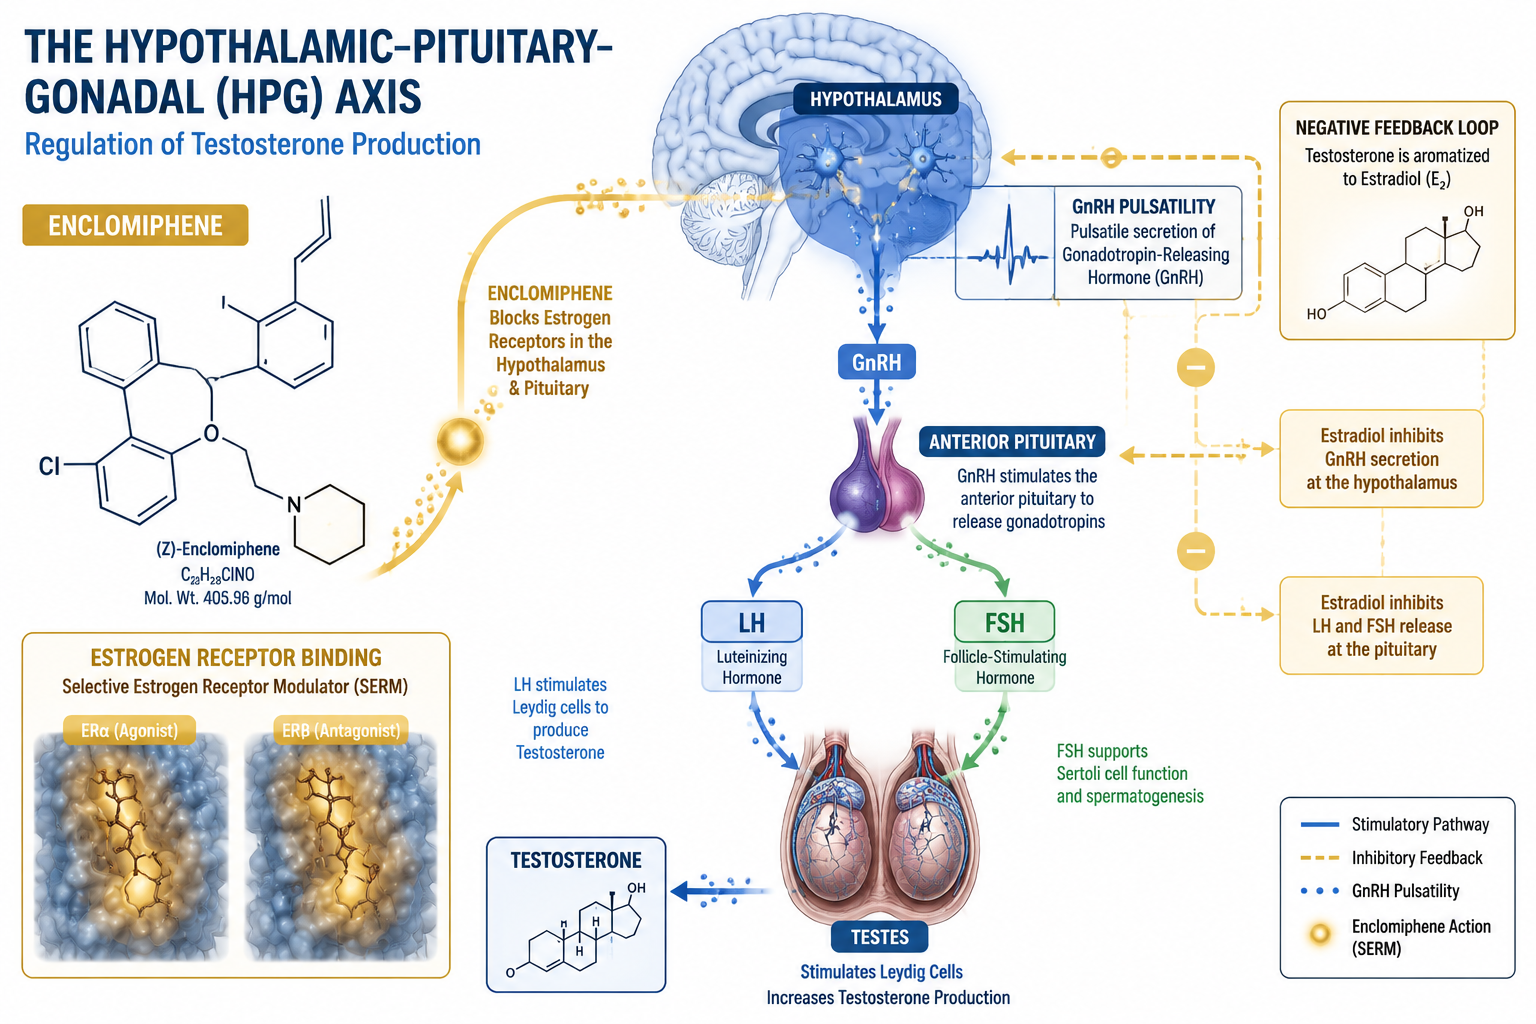
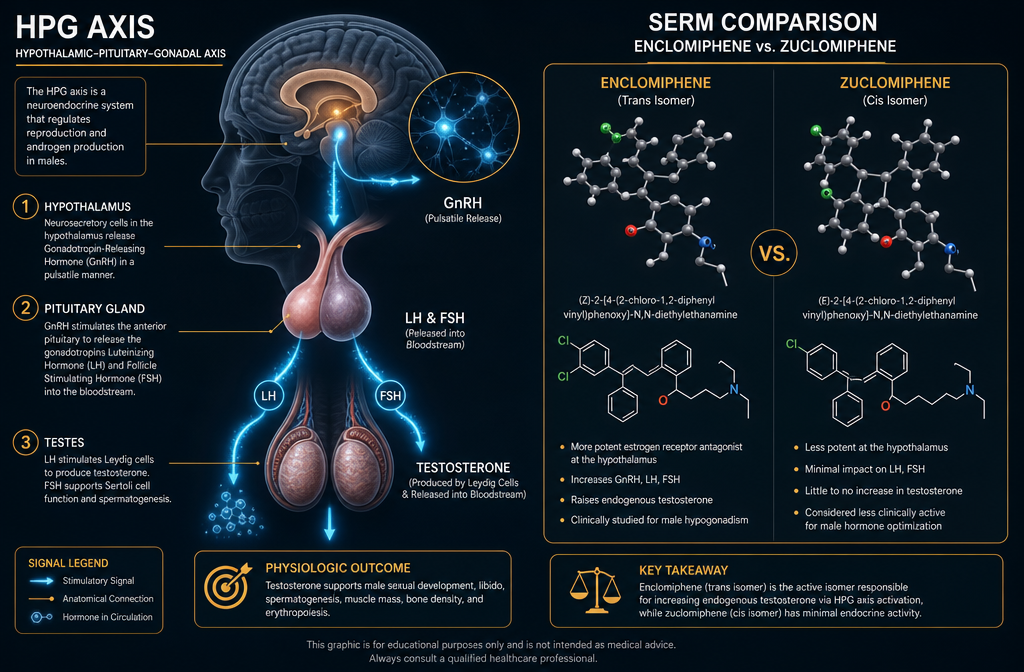
The hypothalamic-pituitary-testicular (HPT) axis does not operate at a flat baseline. GnRH is released from the hypothalamus in discrete bursts, each one triggering a corresponding LH pulse from the pituitary. FSH rises more gradually but still fluctuates. Testosterone, in turn, feeds back to suppress GnRH and LH through two mechanisms: direct androgen feedback and aromatization to estradiol, which exerts its own potent negative feedback at both the hypothalamus and pituitary.
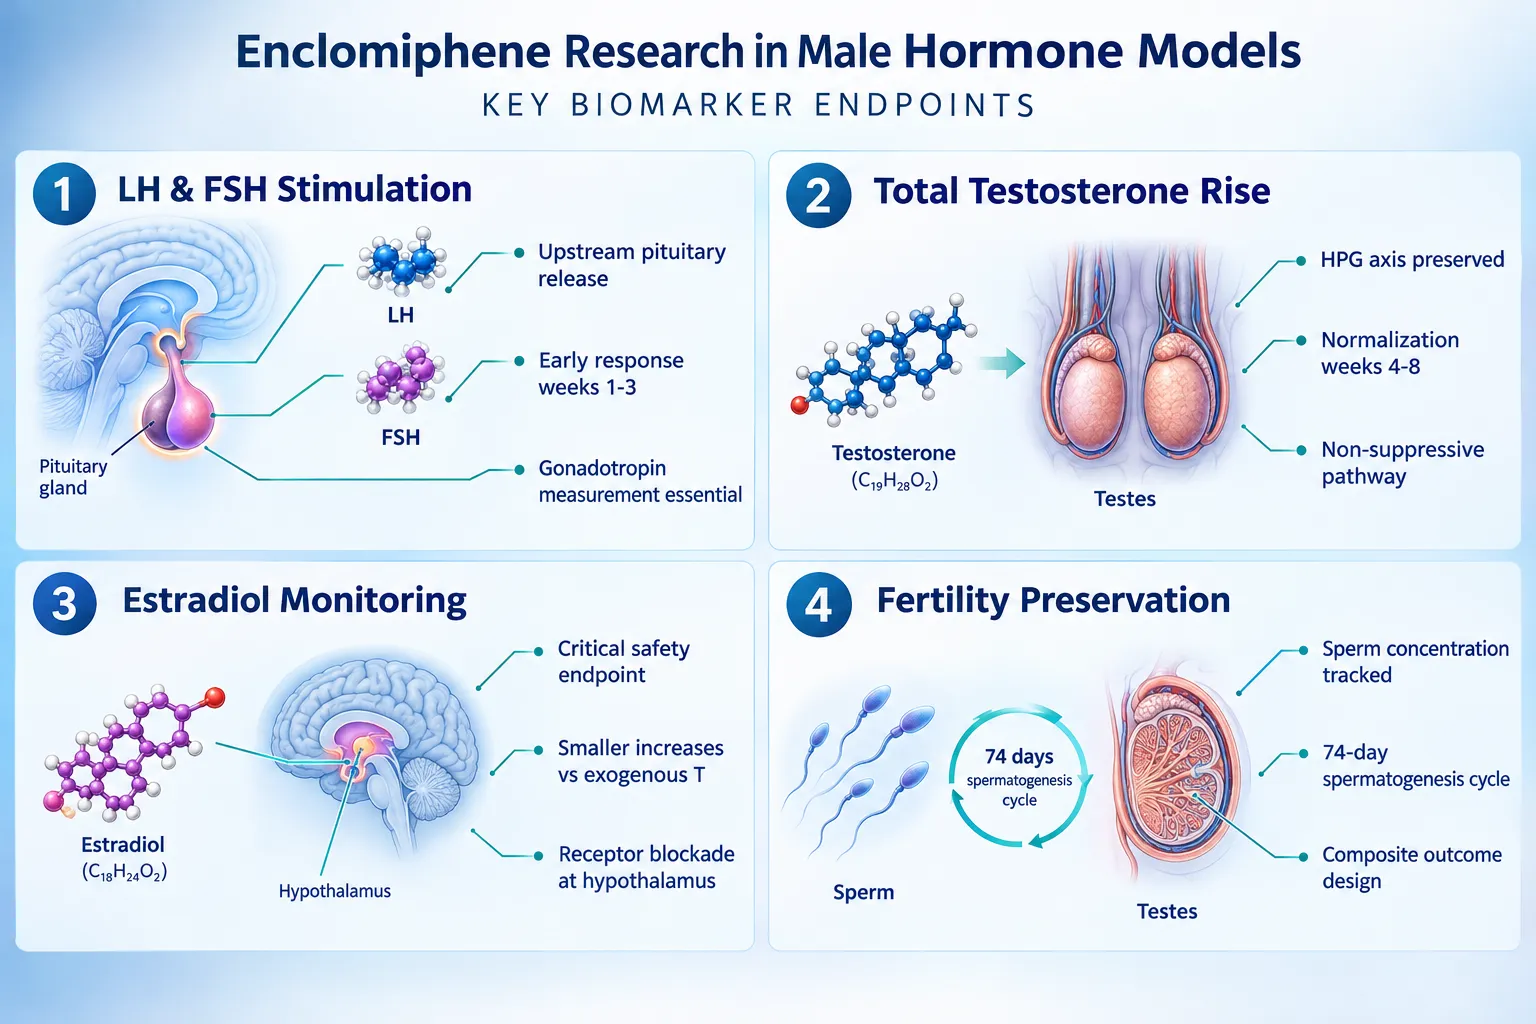
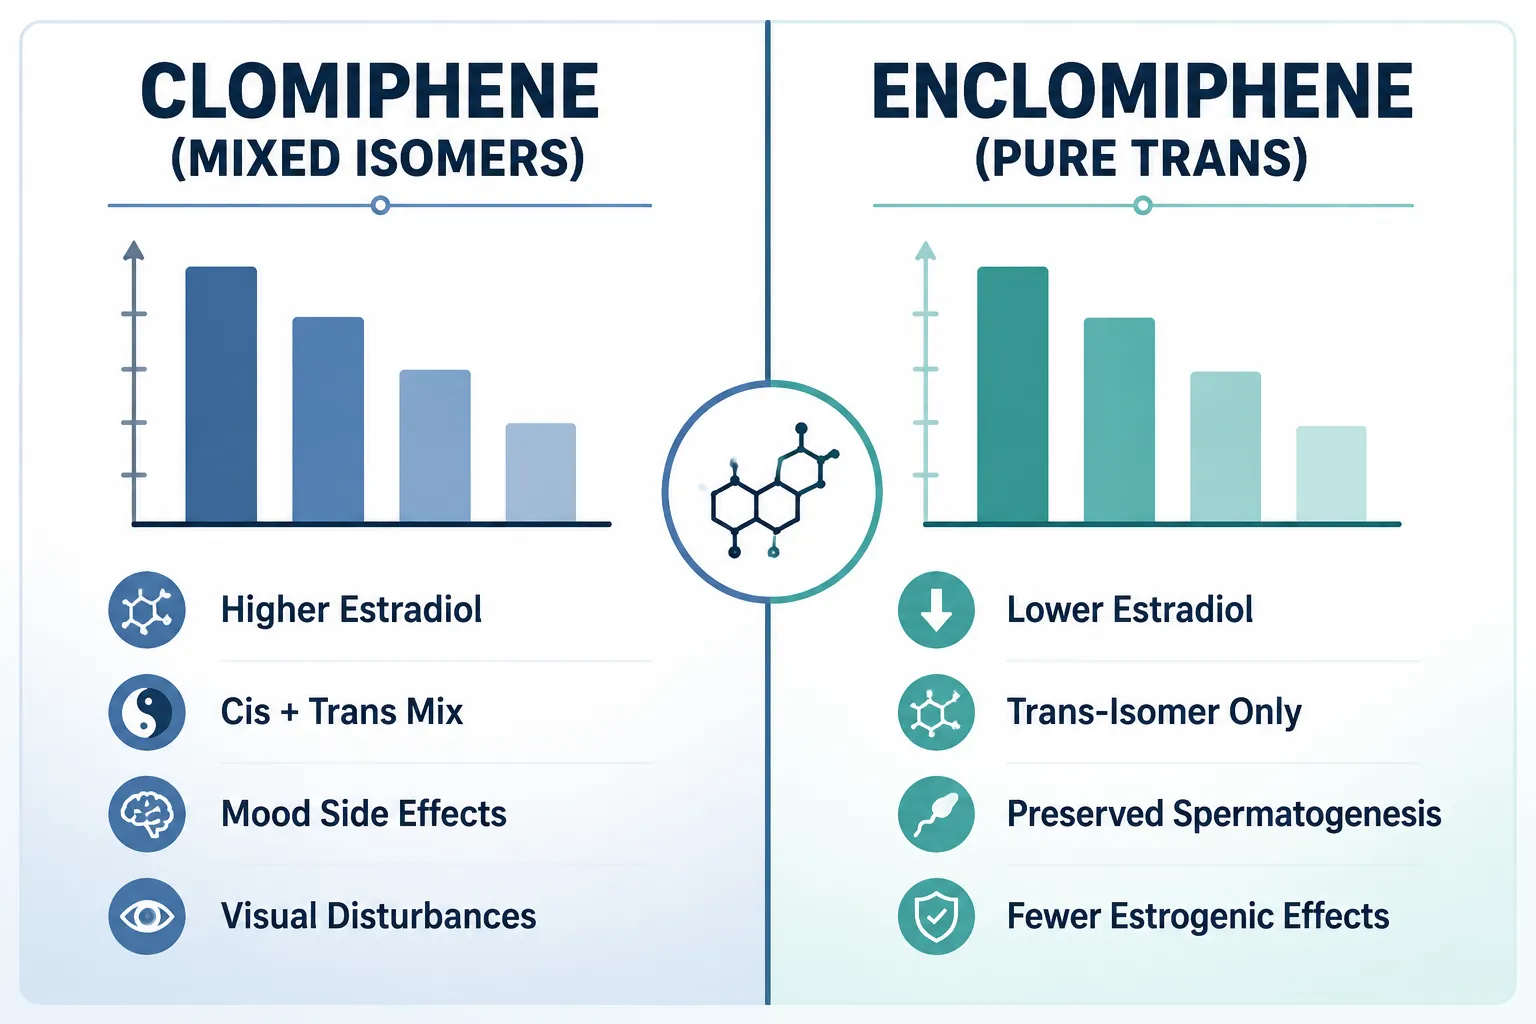
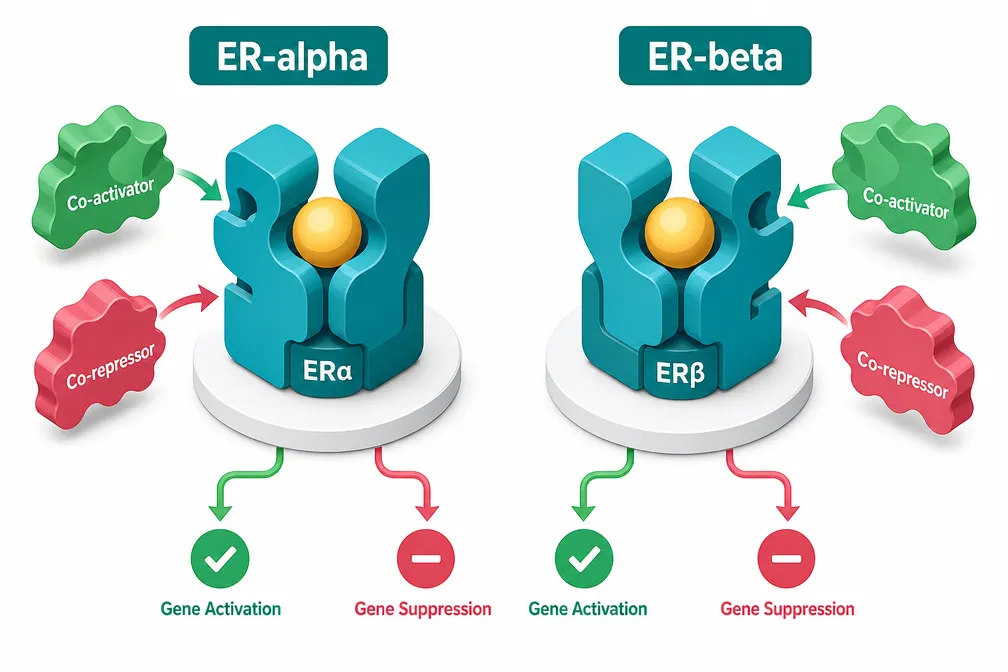
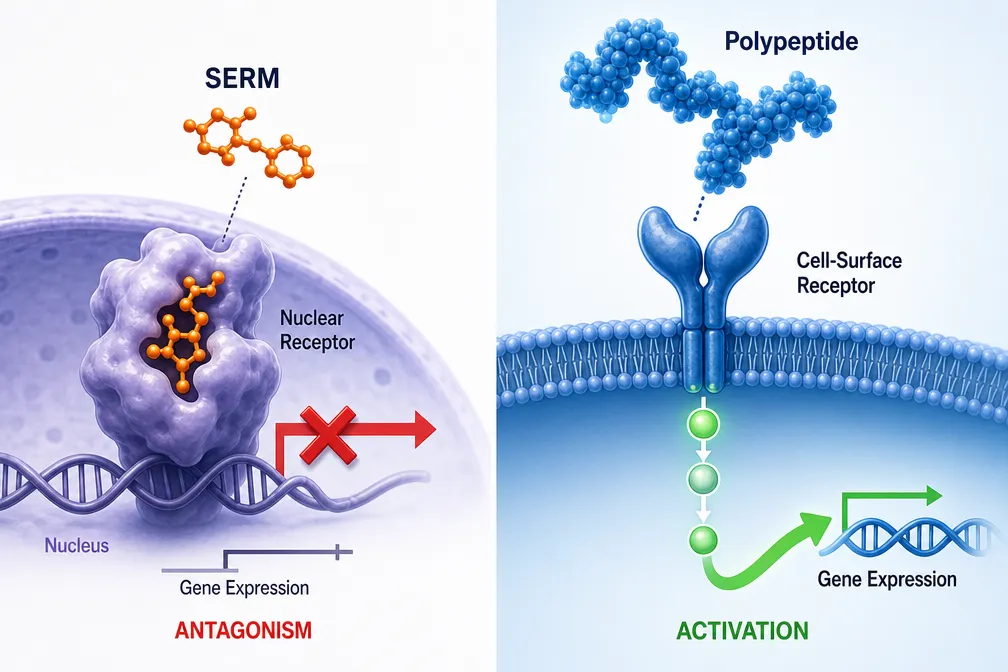
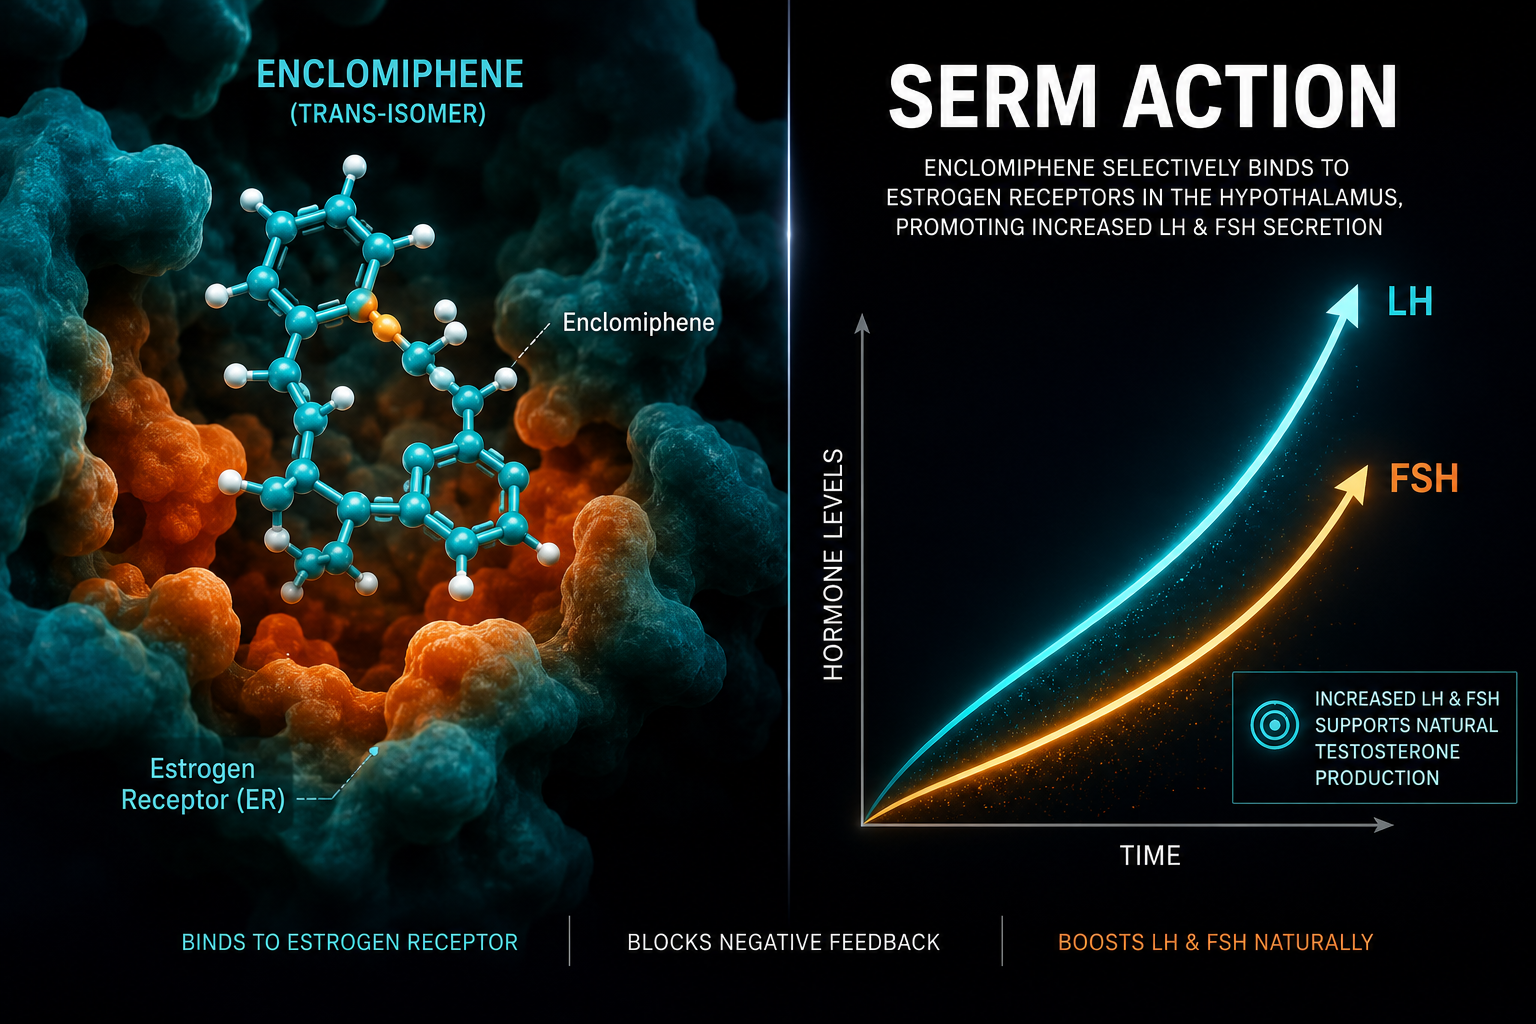
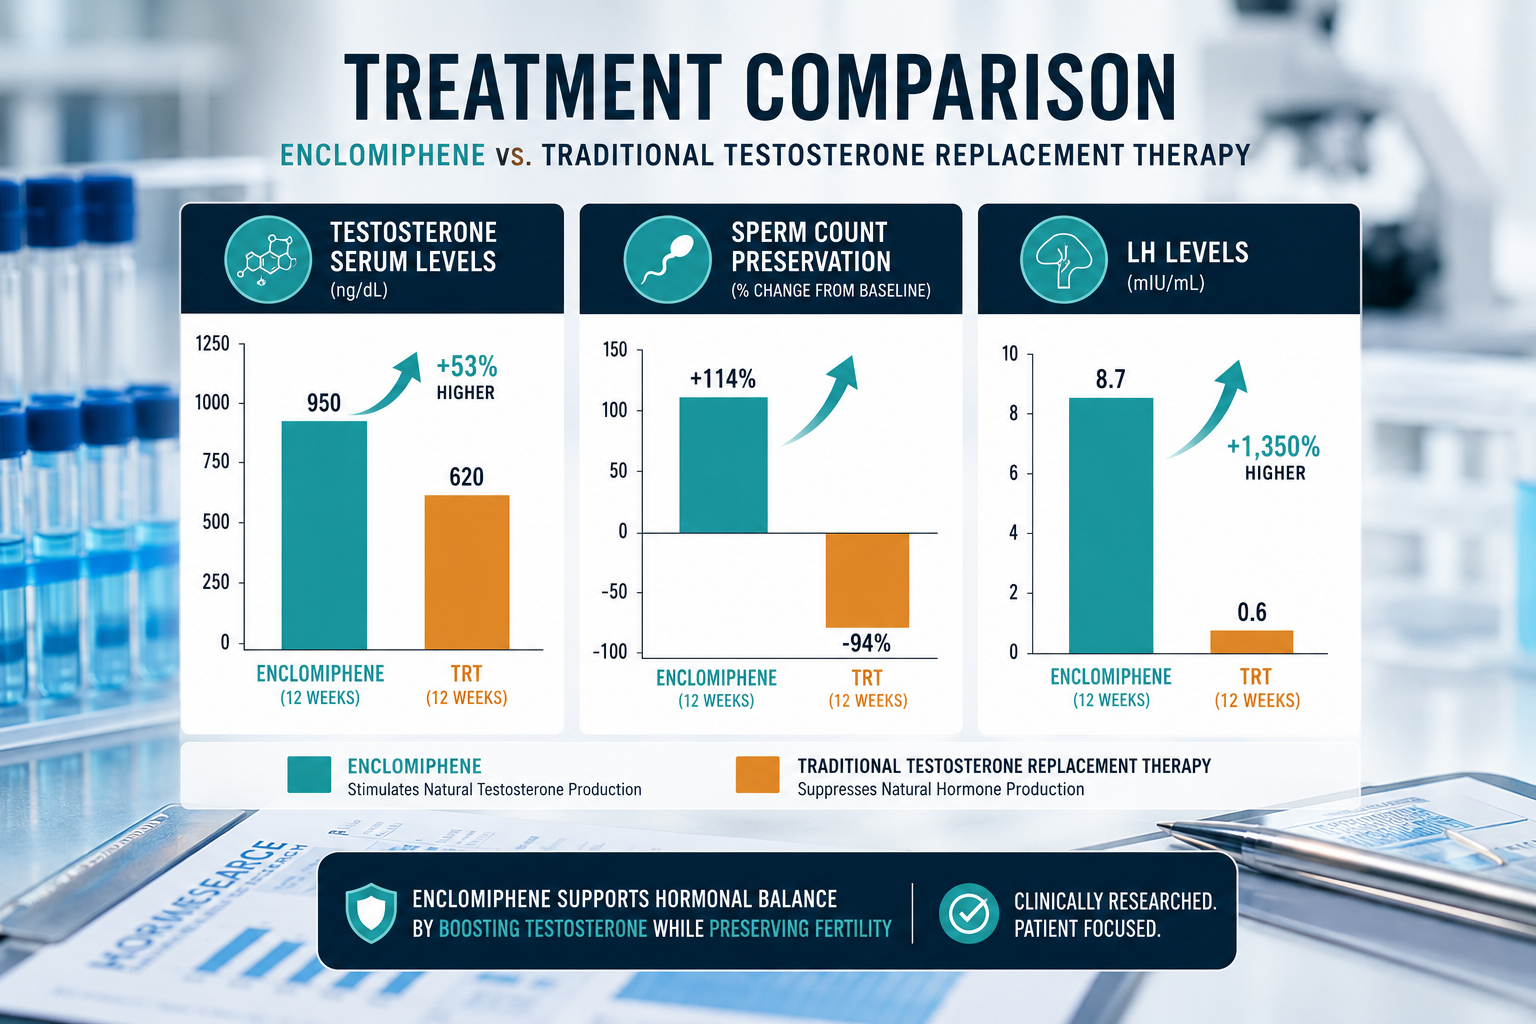
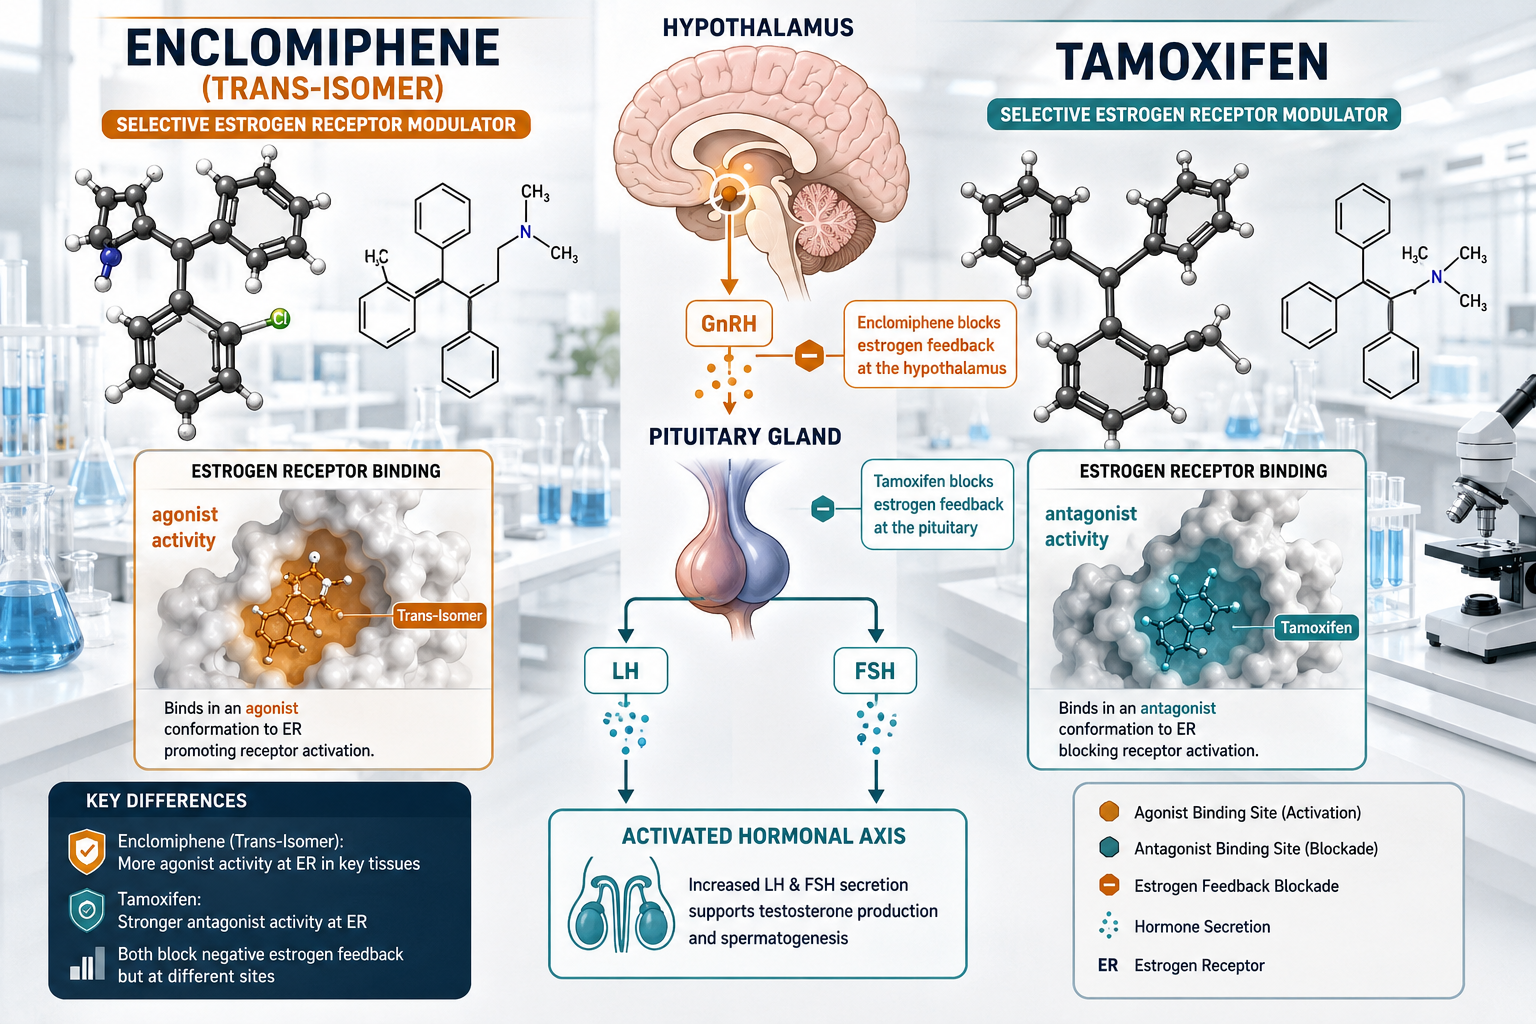
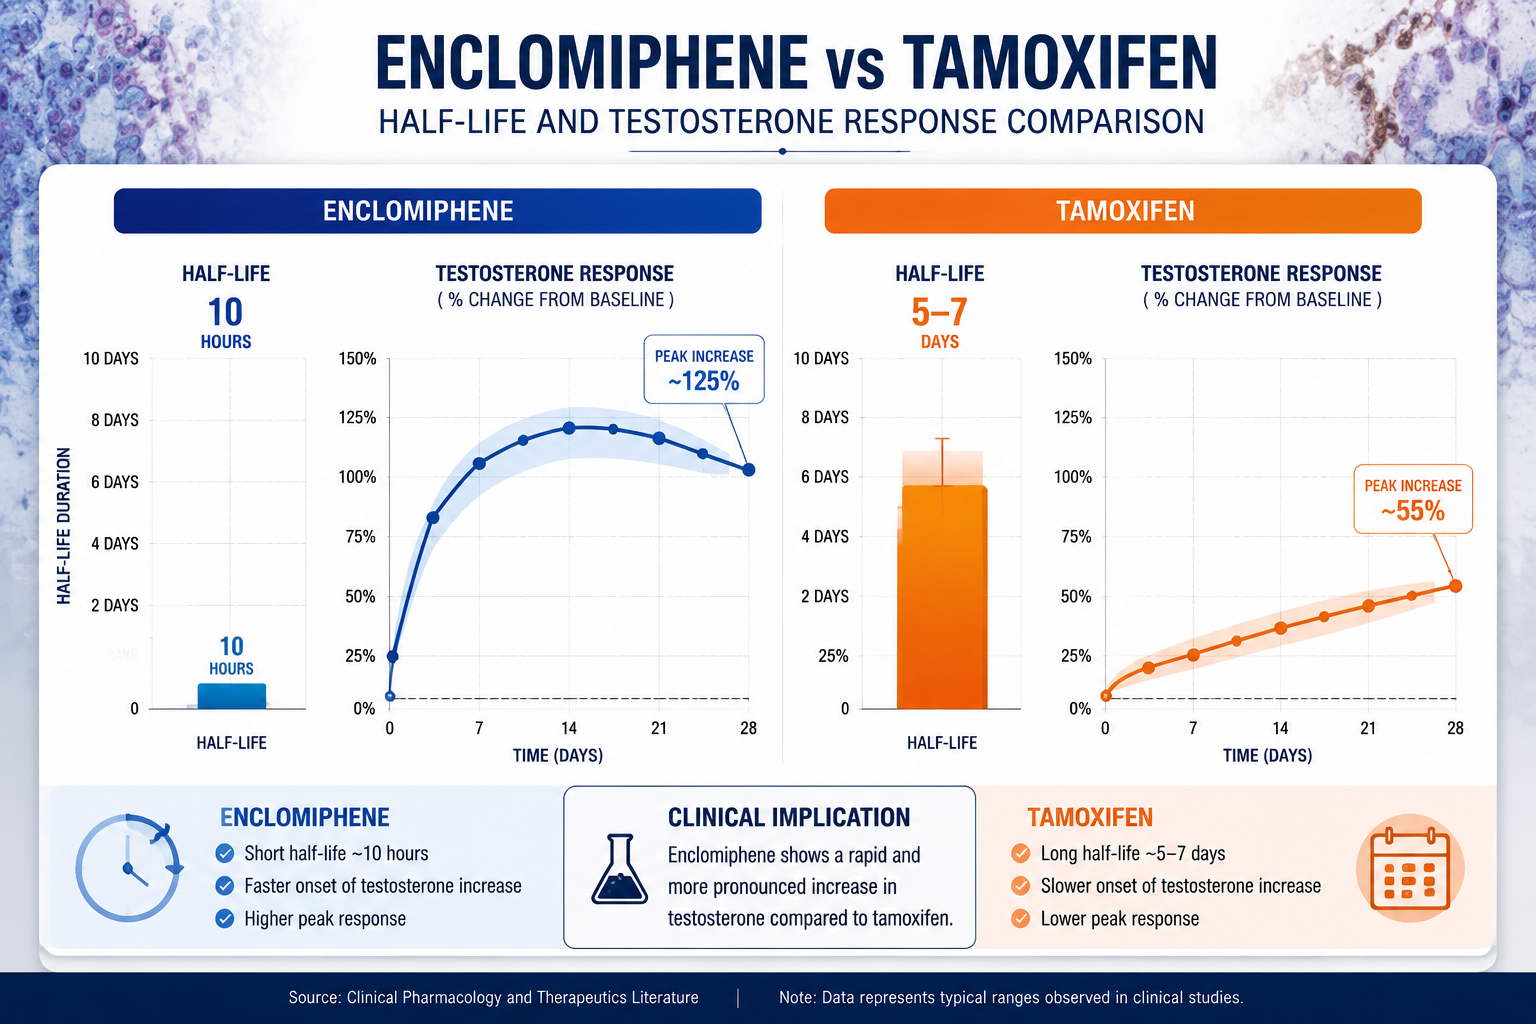
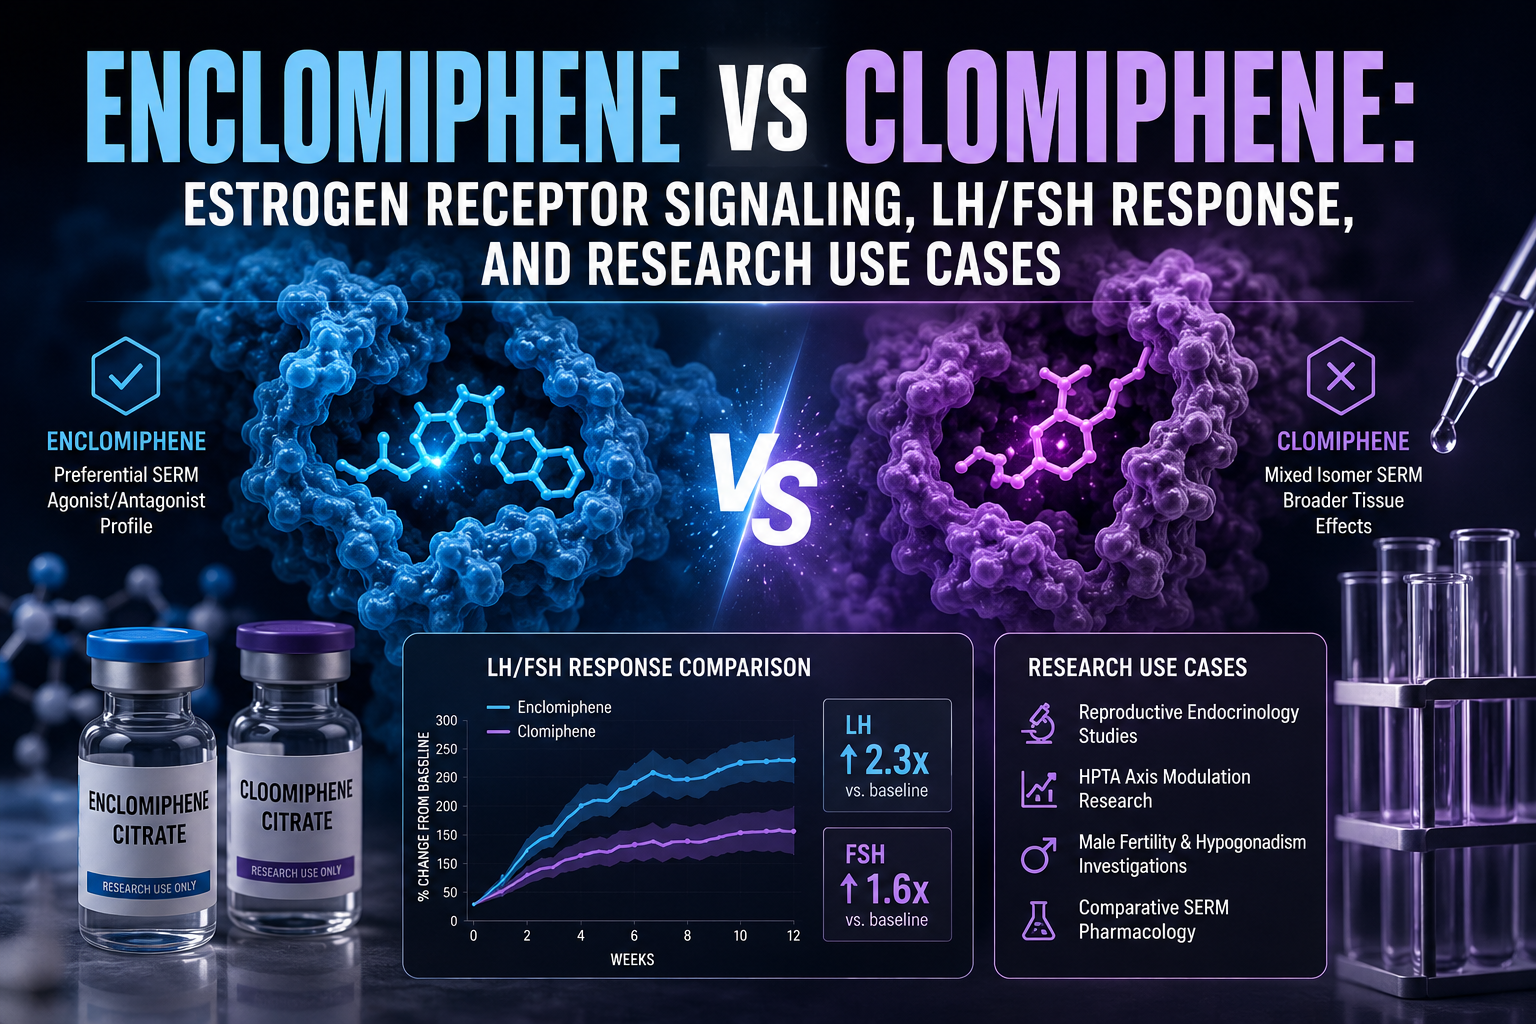
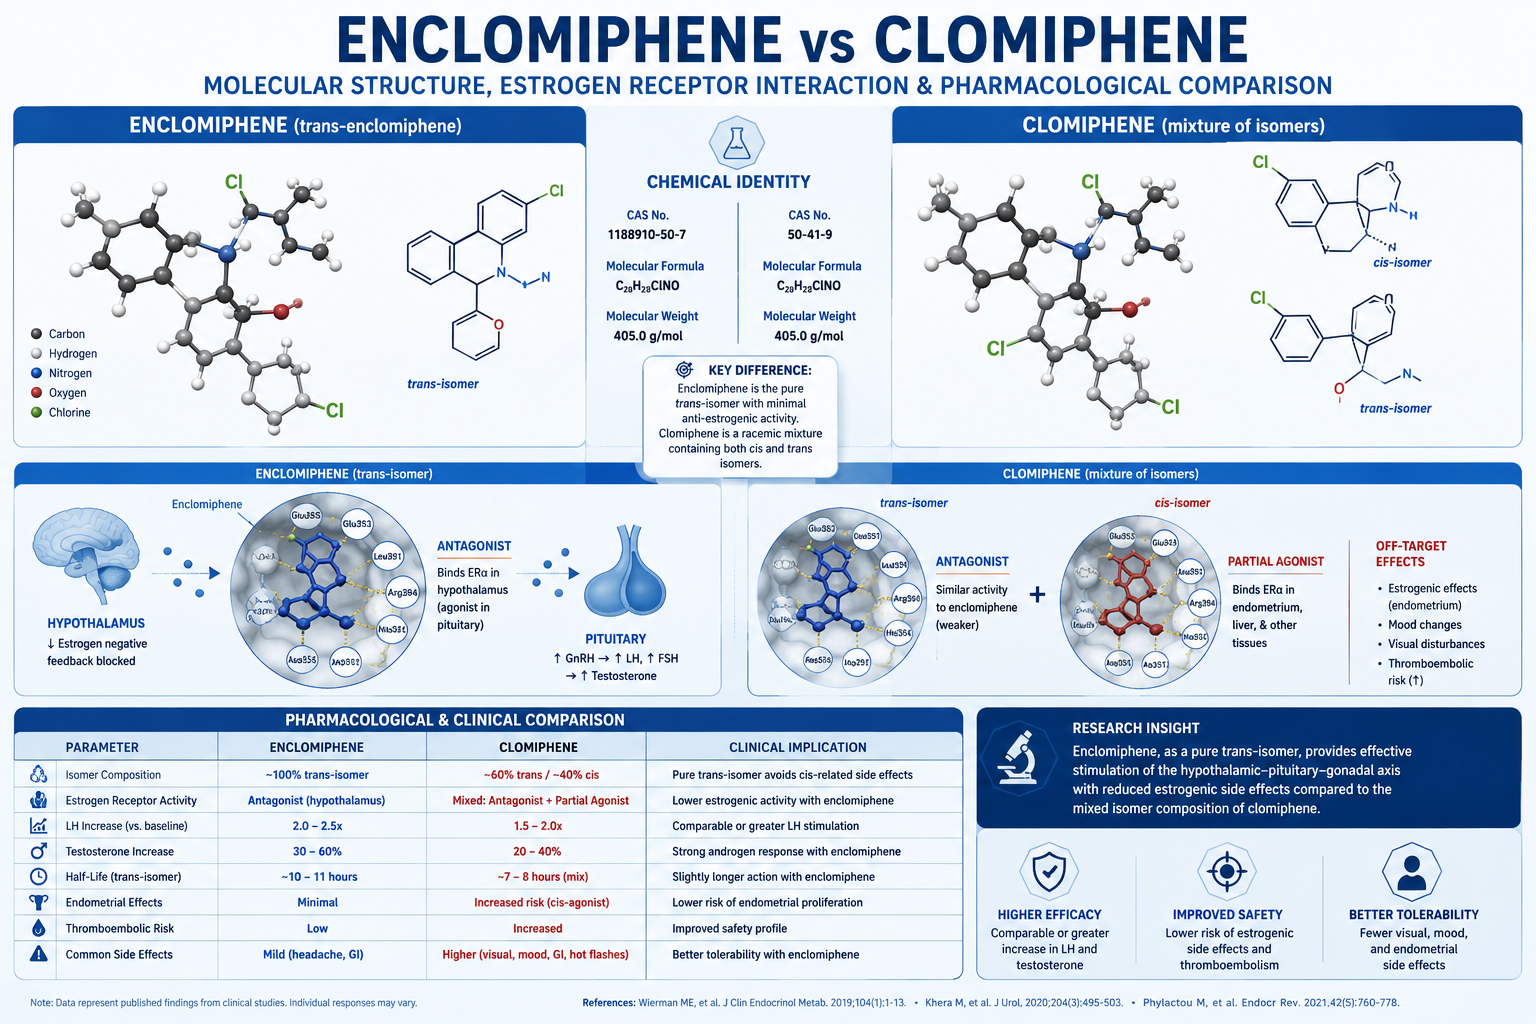
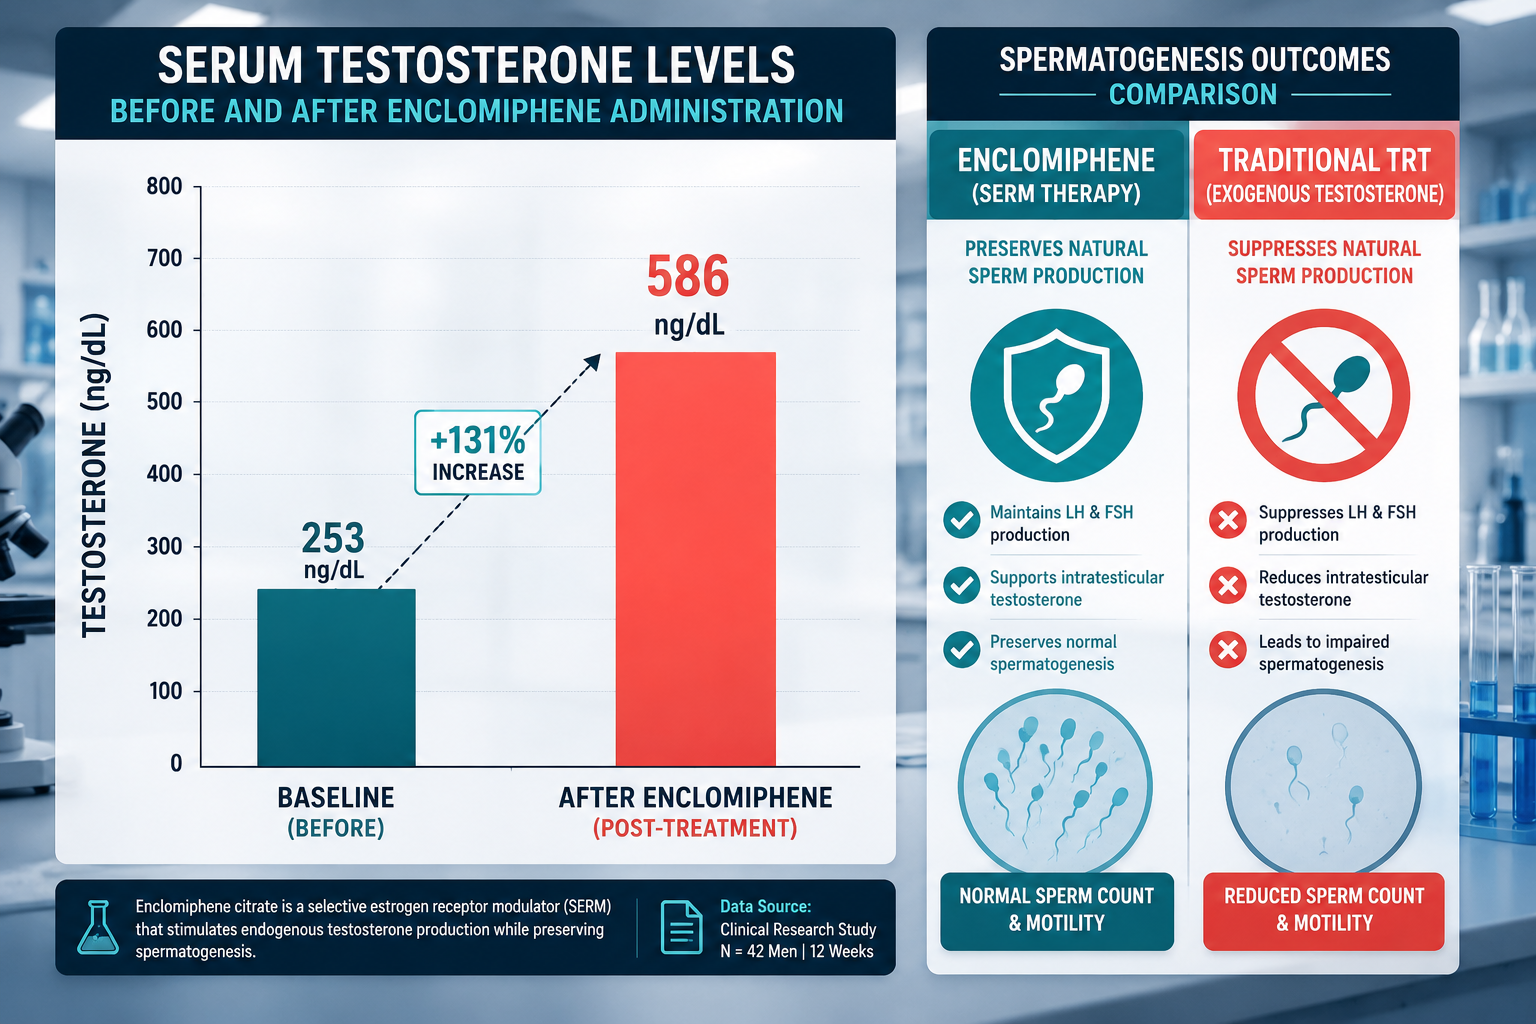
Enclomiphene, the trans-isomer of clomiphene, works by blocking estrogen receptors in the hypothalamus. This reduces the perceived estradiol signal, which the brain interprets as low estrogen, prompting increased GnRH pulsatility and downstream LH and FSH elevation. The result is endogenous testosterone stimulation without suppressing the HPT axis, a key advantage over exogenous testosterone therapy.
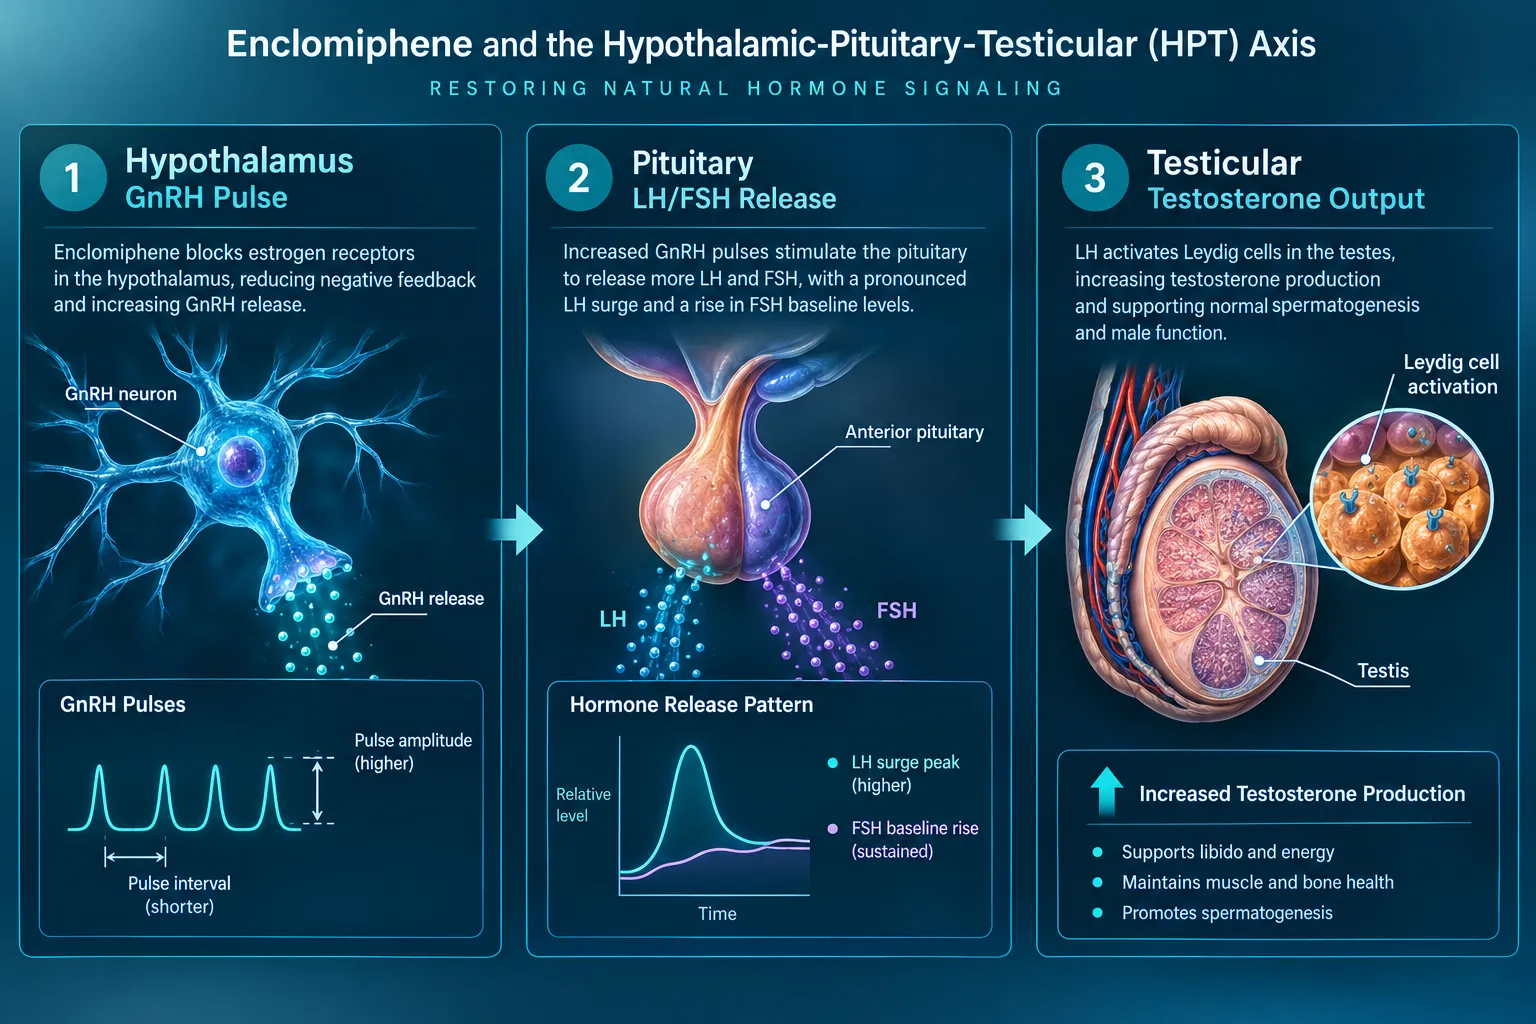
However, this mechanism creates a measurement challenge. The drug acts at the receptor level, not by directly injecting gonadotropins. Its influence on LH pulse amplitude and frequency unfolds over hours and days, not in lockstep with serum drug concentration. An old human study using the en-clomiphene isomer alone found no significant effect on FSH and even a day-8 decrease in LH, a result that highlights how timing, isomer composition, and assay context can dramatically change what gets observed. FDA data further show that LH and FSH remain elevated seven days after dosing begins, meaning the endocrine effect outlasts any single pharmacokinetic peak.
"The drug's receptor-level action means its hormonal footprint can persist long after serum concentration falls, a critical design consideration for any sampling protocol."
The Sampling Design Challenge: Separating Endocrine Feedback From Circadian Variation
The core problem in studying enclomiphene and LH/FSH pulsatility: a sampling design for separating endocrine feedback from circadian variation is that two independent rhythms overlap on the same hormone readout.
Two sources of LH/FSH variation:
| Source | Timescale | Mechanism |
|---|---|---|
| GnRH-driven pulses | Every 60-120 min | Hypothalamic oscillator |
| Circadian rhythm | 24-hour cycle | Sleep, cortisol, melatonin |
| Estradiol feedback | Hours to days | Aromatization of testosterone |
| Enclomiphene receptor blockade | Days to weeks | Estrogen receptor antagonism |
A single morning draw captures one point on a curve that oscillates across all four of these timescales simultaneously. To isolate the drug's contribution, the sampling design must account for each layer.
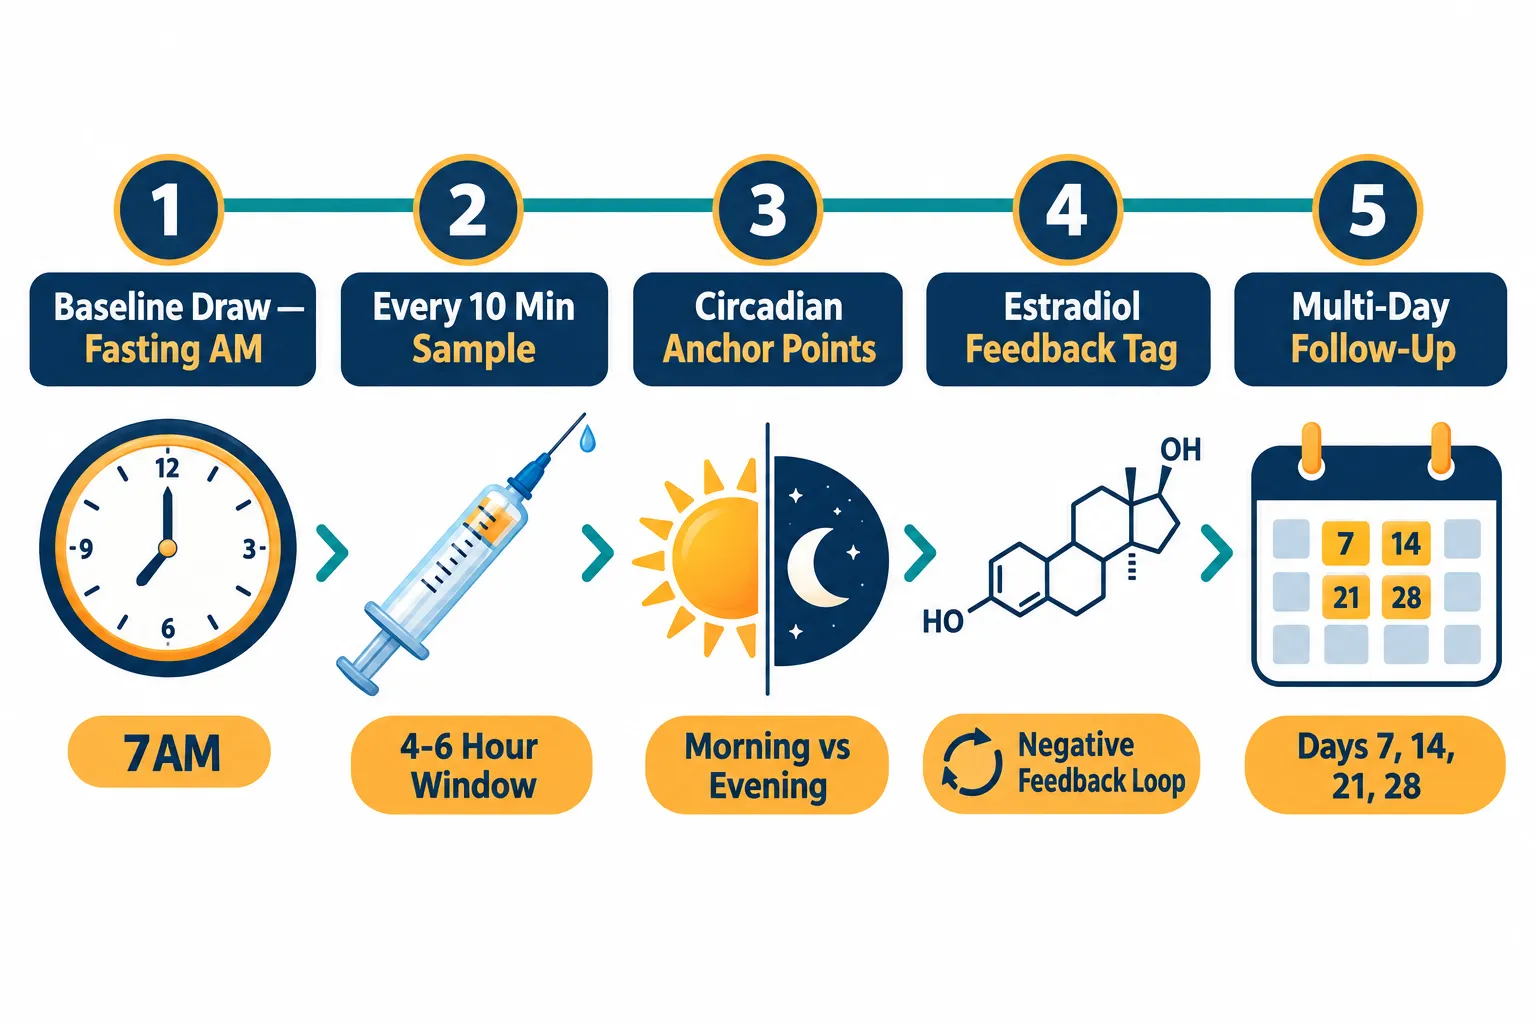
The clearest published guidance on this comes from researchers who specify that blood samples must be collected every 10 minutes for at least 4 to 6 hours to characterize pulsatility properly. This dense-sampling window allows deconvolution algorithms to separate pulse frequency from pulse amplitude, the two parameters most relevant to understanding HPT axis responsiveness under enclomiphene.
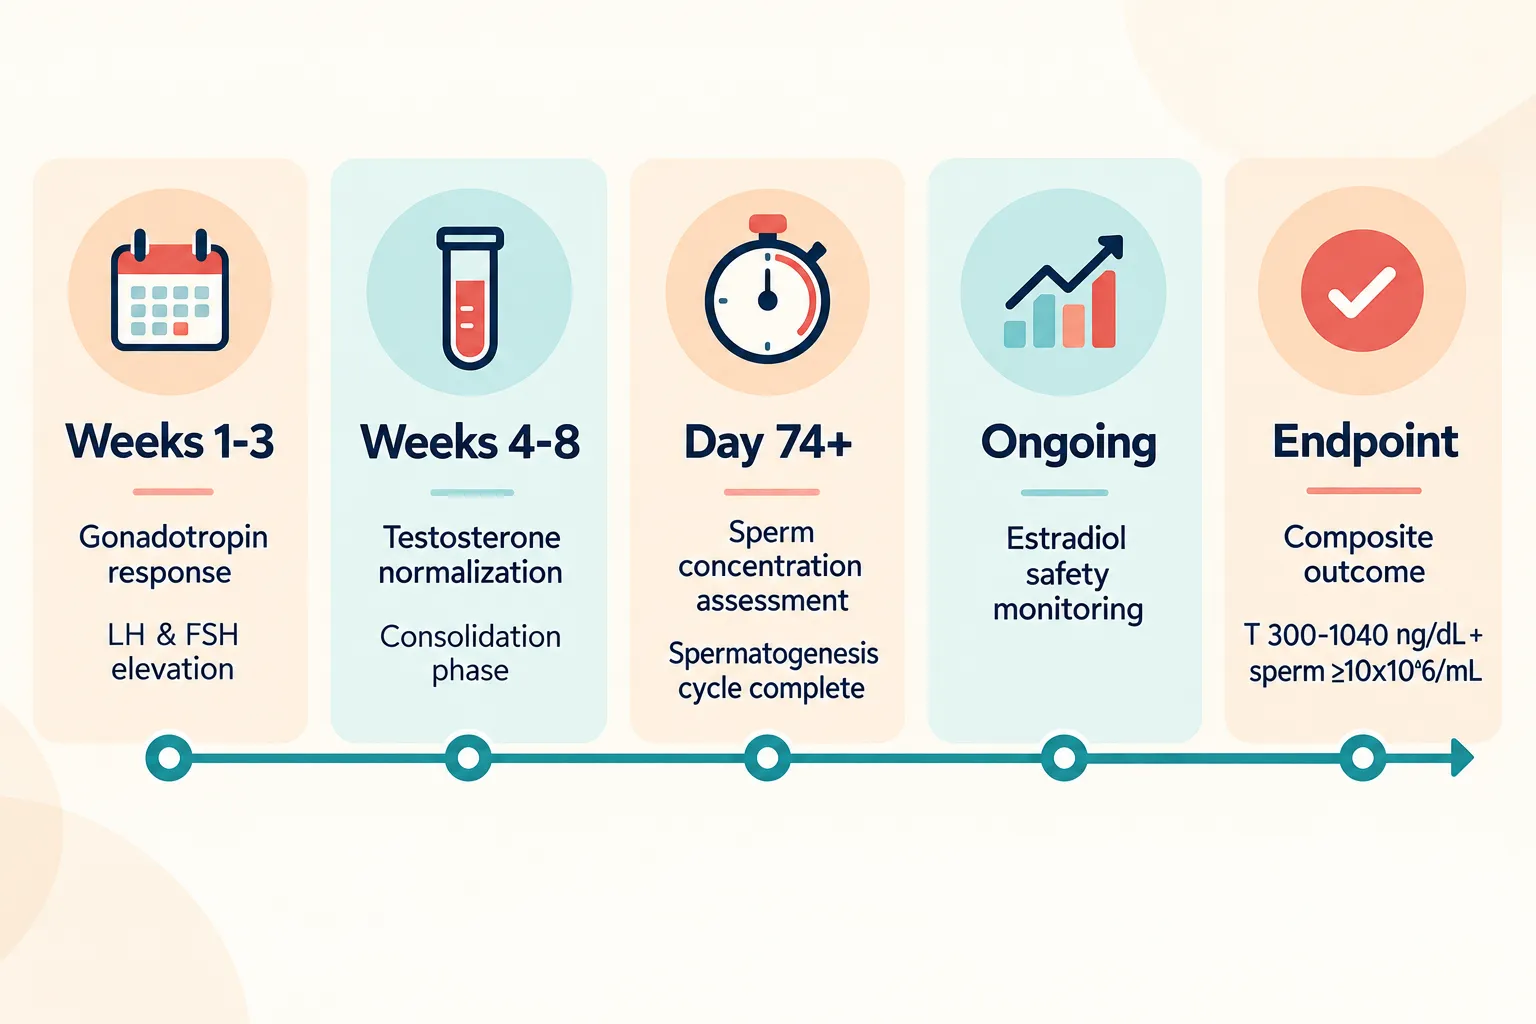
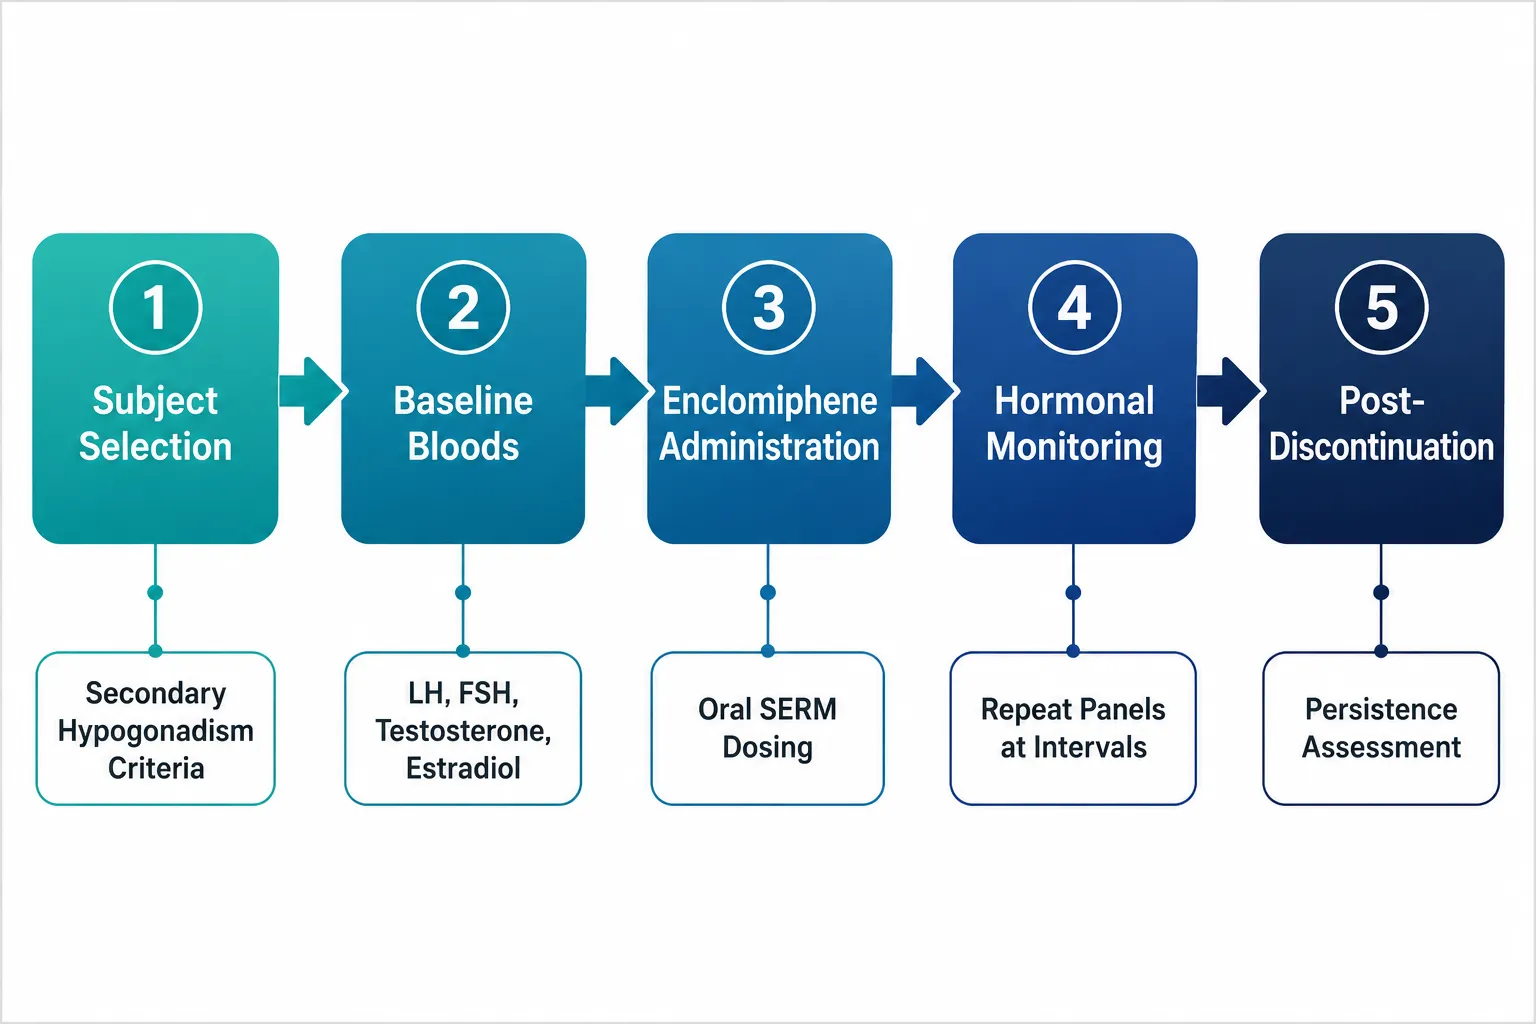
A structured longitudinal design used in a JCEM clomiphene study enrolled 12 healthy men aged 25 to 38 and collected samples at baseline plus days 7, 14, 21, 28, 30, 32, 35, 37, 44, 51, and 58. This schedule tracked hormone trajectories during exposure and through washout, providing a practical template for multi-day characterization. Importantly, it also illustrates how combining frequent within-day sampling with multi-day follow-up can distinguish acute pulsatility changes from sustained feedback-loop adaptations.
For researchers and clinicians working with peptide-based hormonal interventions, understanding pulsatile dynamics is relevant beyond enclomiphene alone. Compounds that interact with growth hormone axes, such as those explored in resources comparing Sermorelin vs Tesamorelin or examining Tesamorelin peptide benefits, face analogous sampling challenges because growth hormone is also secreted in pulses with strong circadian anchoring.
Practical Protocol Considerations for 2026 Research and Clinical Monitoring
Translating sampling theory into a workable protocol requires decisions about anchor points, assay selection, and population context.
Recommended protocol elements:
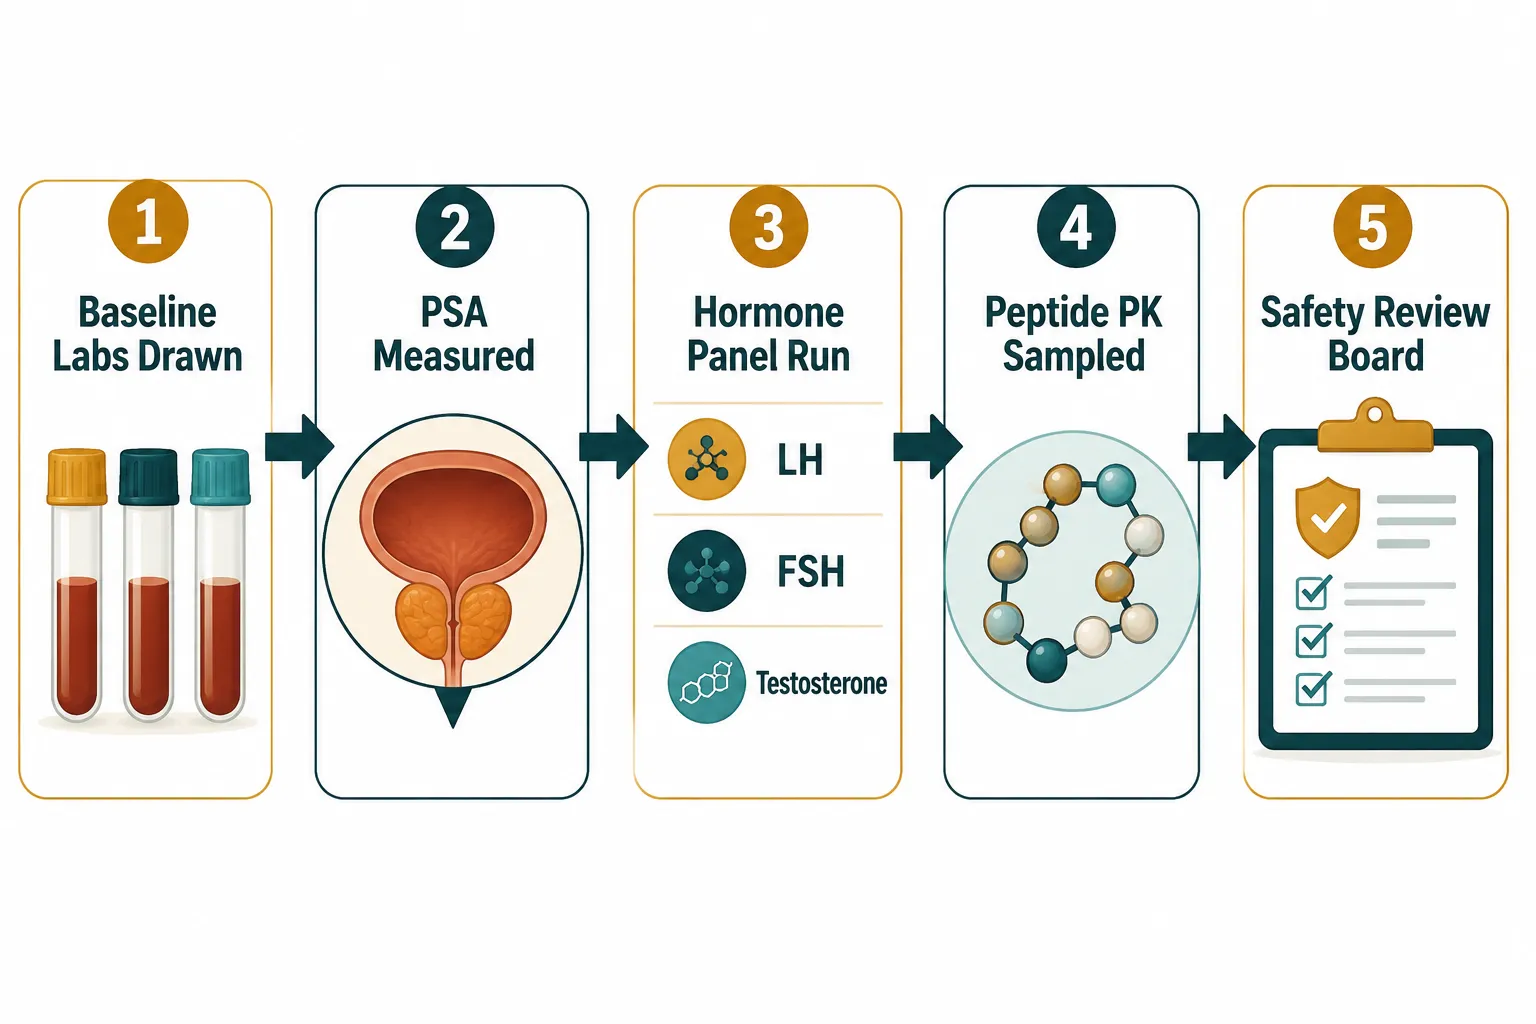
- Circadian anchor: Fix the sampling window to the same clock time across all subjects (typically 07:00-13:00) to control for diurnal LH variation.
- Fasting state: Require overnight fasting before each dense-sampling session to reduce metabolic noise.
- Estradiol co-measurement: Collect estradiol at every timepoint alongside LH and FSH; this allows real-time assessment of negative feedback strength.
- Baseline characterization: Run at least one dense-sampling session before enclomiphene initiation to establish individual pulse parameters.
- Multi-day follow-up draws: Add single-timepoint draws on days 7, 14, 21, and 28 to track trajectory between dense sessions.
A 2026 British Society of Sexual Medicine position statement reviewed a cohort of 78 patients and found no statistically significant pre-versus-post differences in testosterone, LH, FSH, or semen parameters, a finding that underscores how much population selection and sampling design influence outcome interpretation. When dense pulsatility data are absent, retrospective cohort analyses like this one cannot distinguish a true null effect from a measurement artifact caused by sparse or poorly timed draws.
The same 2026 position statement supports enclomiphene-class therapy as a fertility-preserving option in men, keeping the clinical stakes of accurate monitoring high. A 2026 review on clomiphene mechanisms reinforces that these agents are used to increase LH, FSH, and testosterone in eugonadal men, a population where baseline pulsatility is already robust and where detecting drug-driven changes requires especially precise sampling.
Practical 2026 clinical guidance continues to recommend morning fasting hormone draws and baseline-plus-follow-up monitoring. These are reasonable heuristics for routine care, but they are not validated pulsatility protocols. The gap between clinical convenience and research-grade measurement is where most interpretive errors occur.
For those interested in how other peptide compounds interact with hormonal feedback loops, resources on CJC-1295 IPA 10mg and the question of whether Ipamorelin and CJC-1295 can be taken together provide useful context on how pulsatile growth hormone secretagogues are timed relative to endogenous rhythms. Similarly, Tesamorelin dosage per day discussions illustrate how dose timing intersects with circadian biology in a directly analogous way.
Mitochondrial peptides such as those discussed in the MOTS-C and Elamipretide resource operate through different axes but reinforce the broader principle that timing and biological rhythm are inseparable from endpoint interpretation.
Conclusion
Accurate interpretation of enclomiphene's effects on the HPT axis depends entirely on how and when hormone data are collected. Enclomiphene and LH/FSH pulsatility: a sampling design for separating endocrine feedback from circadian variation is not a theoretical concern, it is a practical barrier to valid conclusions in both clinical trials and individual patient monitoring.
Actionable next steps for researchers and clinicians in 2026:
- Replace single-timepoint draws with dense 10-minute sampling sessions of at least 4 to 6 hours when characterizing individual pulsatility responses.
- Always co-measure estradiol to quantify the negative feedback contribution independently from the drug effect.
- Anchor all sampling sessions to the same circadian time window to eliminate diurnal confounding.
- Adopt multi-day follow-up schedules modeled on published longitudinal designs to track trajectory, not just peak response.
- Interpret retrospective cohort data cautiously when dense pulsatility sampling was not part of the original design.
The biology of pulsatile gonadotropin secretion is well understood. The gap that remains is methodological, and closing it starts with a better sampling design.