Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu
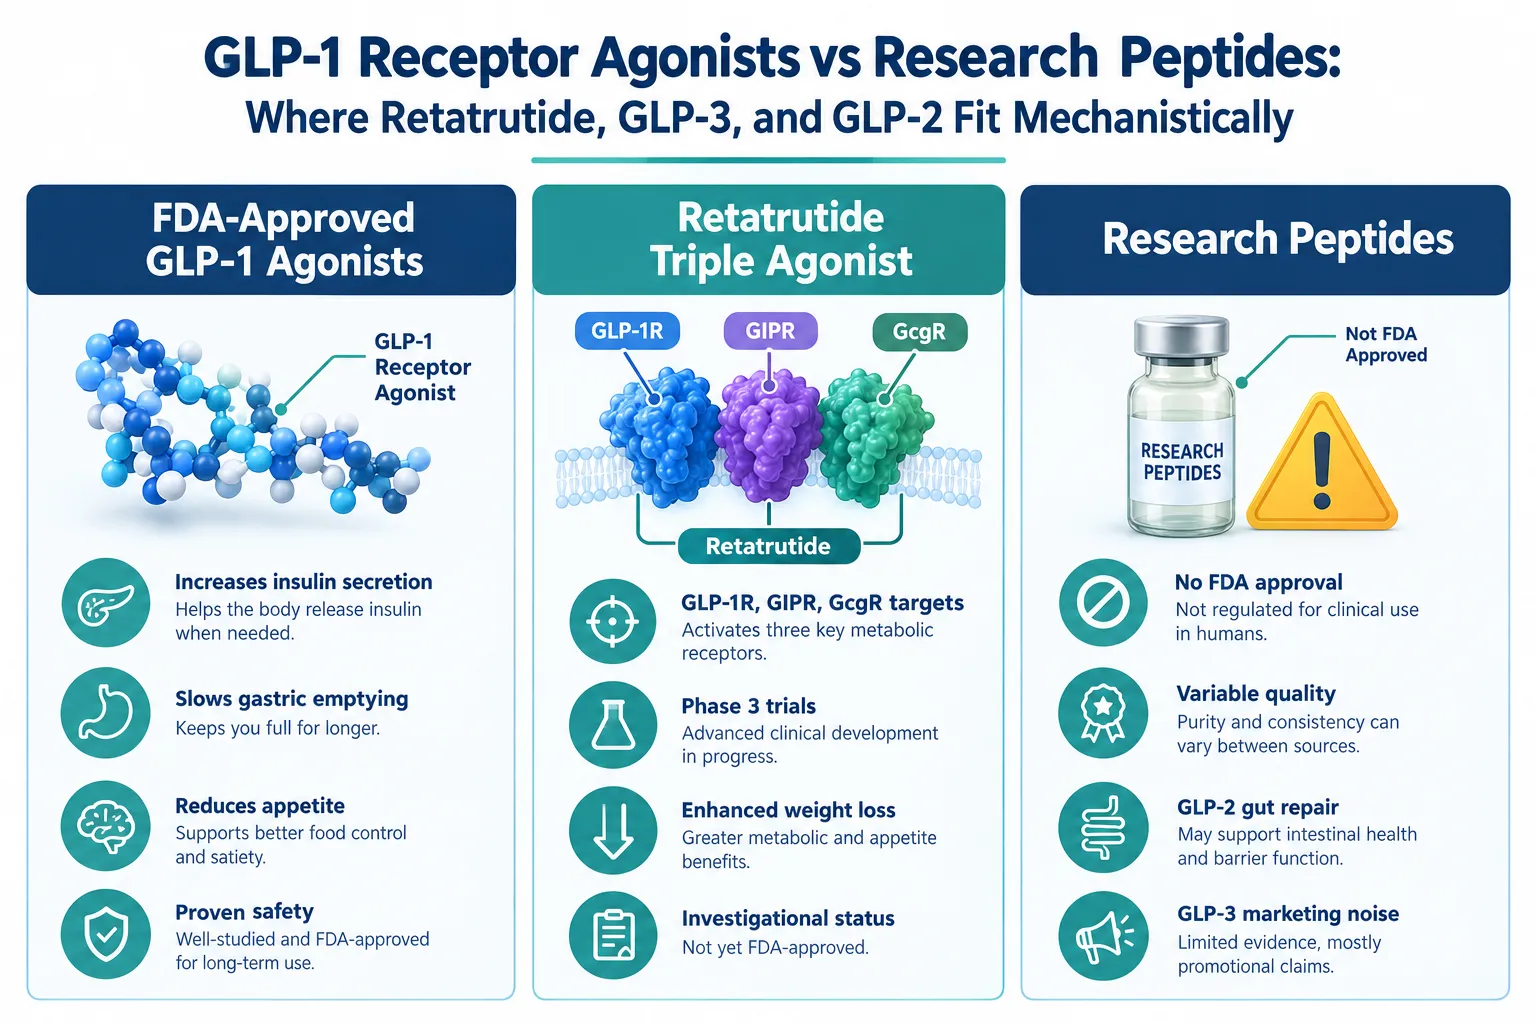
GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically

GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically

September 14, 2026/0 Comments/in Uncategorized/by

Fewer than 5% of people with obesity currently have access to the drug class generating the most clinical excitement since statins, yet the peptide research space has expanded far beyond that single drug class, creating genuine confusion about what is approved, what is investigational, and what remains largely theoretical. Understanding GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically is not just an academic exercise. It shapes how clinicians, researchers, and informed readers interpret headlines, evaluate compounds, and distinguish between a regulated medicine and a laboratory tool.

Key Takeaways

  • GLP-1 receptor agonists are an established, FDA-approved drug class; retatrutide is a next-generation triple agonist still moving through Phase 3 trials as of 2026.
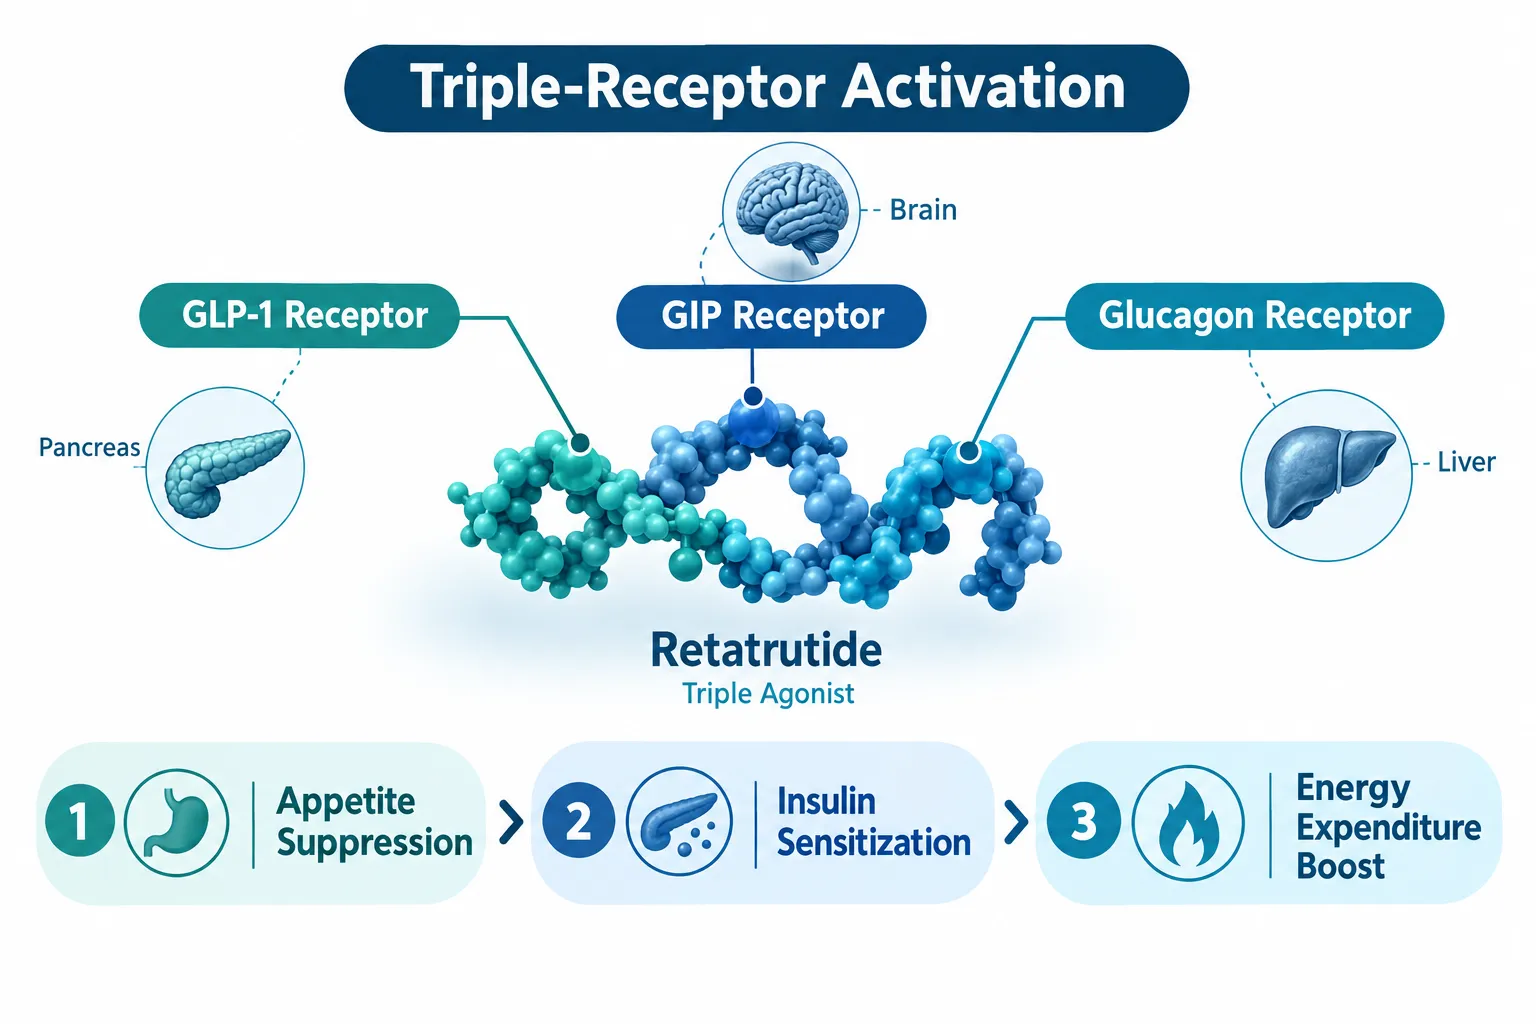
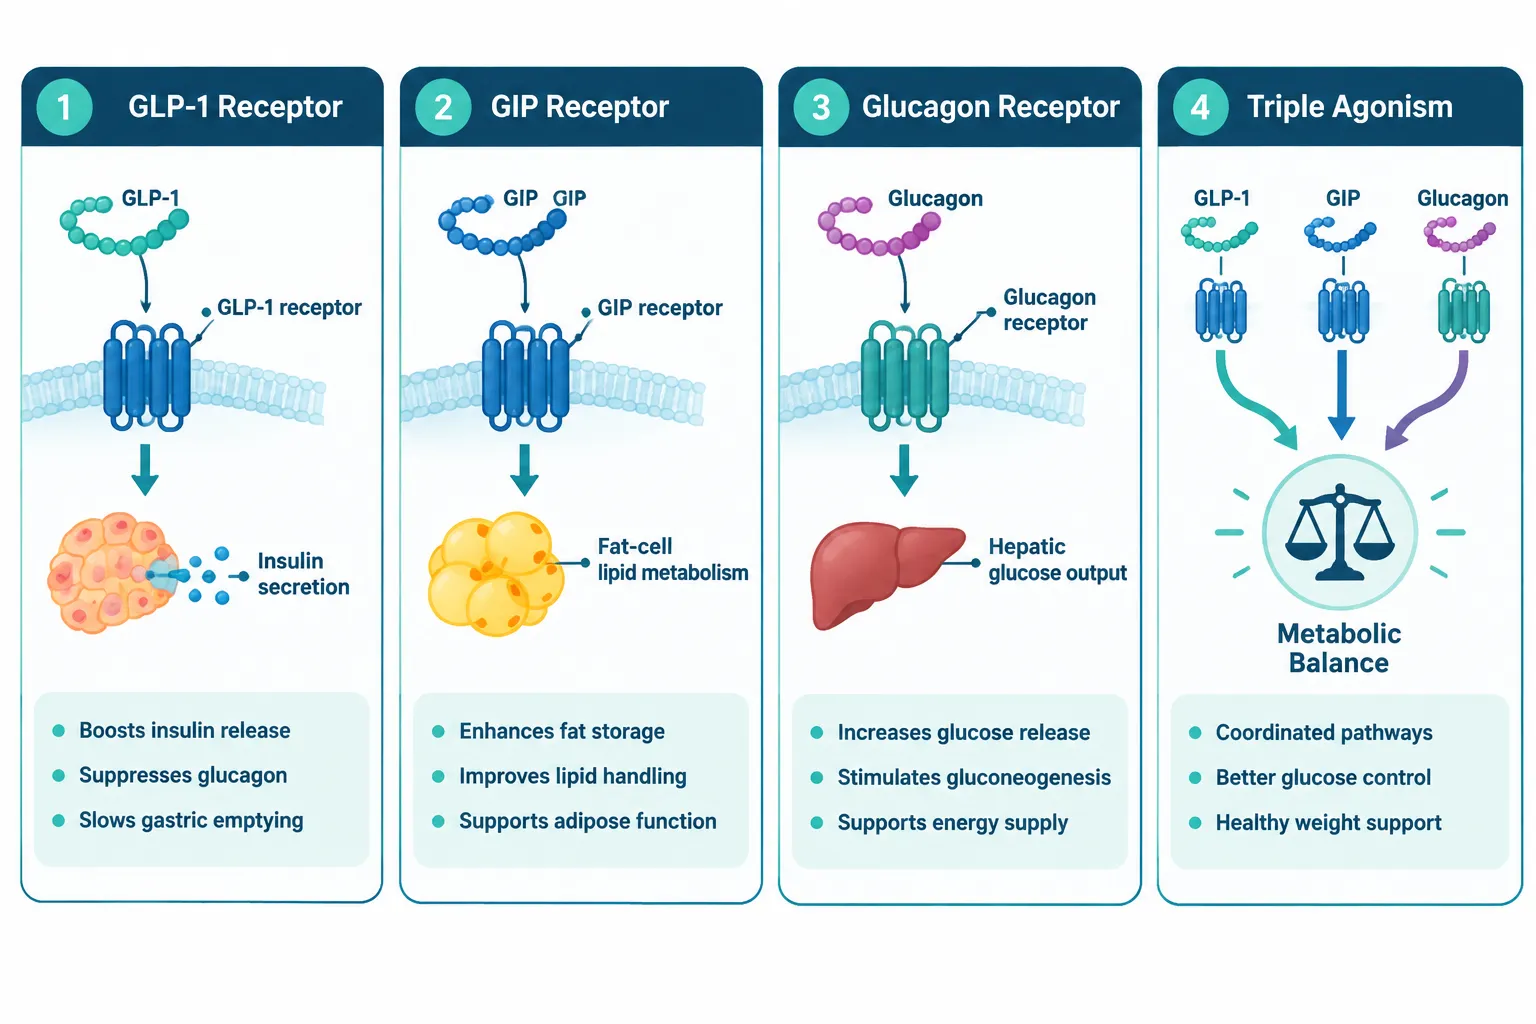
  • Retatrutide targets three receptors (GLP-1R, GIPR, and GcgR simultaneously), producing weight-loss results that significantly exceed standard GLP-1 monotherapy in Phase 2 data.
  • GLP-2 is a structurally related peptide with a distinct, gut-focused mechanism; its agonists are approved for specific intestinal conditions, not obesity.
  • "GLP-3" does not currently represent a validated receptor class; the term is largely used in marketing contexts and should be treated with caution.
  • Research peptides occupy a separate regulatory and mechanistic category from approved GLP-1 drugs, and the distinction matters for both safety and scientific accuracy.

What Defines a GLP-1 Receptor Agonist

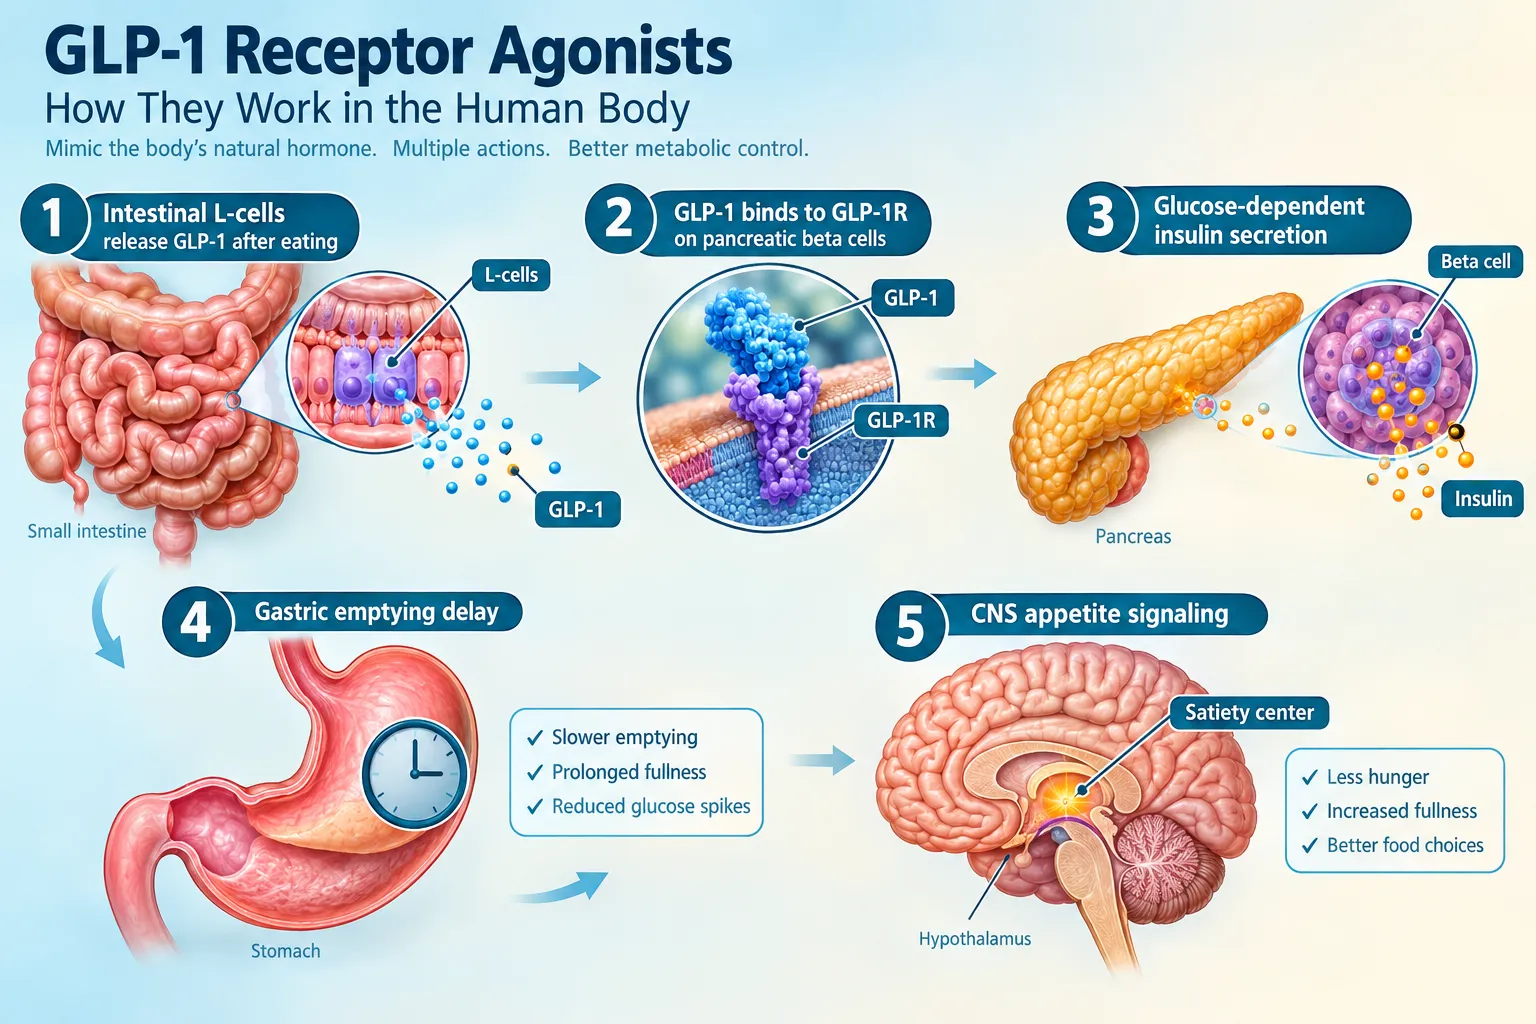
GLP-1 (glucagon-like peptide-1) is an incretin hormone released from intestinal L-cells after eating. It binds the GLP-1 receptor (GLP-1R) to stimulate glucose-dependent insulin secretion, suppress glucagon, slow gastric emptying, and reduce appetite through central nervous system signaling.

Approved GLP-1 receptor agonists, including semaglutide and liraglutide, are synthetic analogs engineered for extended half-lives. They are regulated medicines with defined dosing, safety profiles, and clinical indications. In obesity trials, semaglutide produces mean body-weight reductions of approximately 15% over 68 weeks, a benchmark that defined the class.
What Defines a GLP-1 Receptor Agonist

The key mechanistic point: these drugs act on a single receptor. Their benefits, glycemic control, modest cardiovascular risk reduction, and weight loss, flow from that one target. This single-receptor architecture is precisely what newer compounds like retatrutide are designed to move beyond.

Retatrutide: Where Triple Agonism Changes the Equation

Retatrutide is the clearest example of why the comparison of GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically demands precision. It is not a research peptide in the informal sense. It is an investigational drug in structured clinical development, and its mechanism is meaningfully different from standard GLP-1 monotherapy.

Retatrutide simultaneously activates three receptors:

Receptor Primary Action
GLP-1R Appetite suppression, insulin secretion, gastric slowing
GIPR (GIP receptor) Enhanced insulin response, adipose tissue signaling
GcgR (Glucagon receptor) Increased energy expenditure, thermogenesis, hepatic fat reduction

This triple agonism produced striking Phase 2 results: participants receiving the highest dose achieved mean weight reductions of approximately 24% over 48 weeks, roughly 60% greater than semaglutide benchmarks in comparable timeframes. Responder analysis showed that a substantial proportion of participants lost more than 20% of body weight, a threshold rarely crossed with single-receptor agents.

Beyond weight, Phase 2 data showed meaningful reductions in fasting glucose, triglycerides, LDL particle counts, and blood pressure. These cardiometabolic improvements suggest the glucagon receptor component contributes effects beyond appetite suppression alone.

As of 2026, retatrutide is in Phase 3 trials covering obesity, type 2 diabetes, and non-alcoholic steatohepatitis (NASH). Regulatory submission timelines remain under active review. Researchers tracking this compound can find relevant context on retatrutide clinical trials and the broader retatrutide clinical trial landscape.

For those looking at investigational compound options, buy Reta online resources and buy Reta peptide listings are available for research purposes, distinct from clinical use.

GLP-2 and GLP-3: Mechanistic Niches and Marketing Noise
GLP-2 and GLP-3: Mechanistic Niches and Marketing Noise

GLP-2: A Real Peptide With a Distinct Gut Role

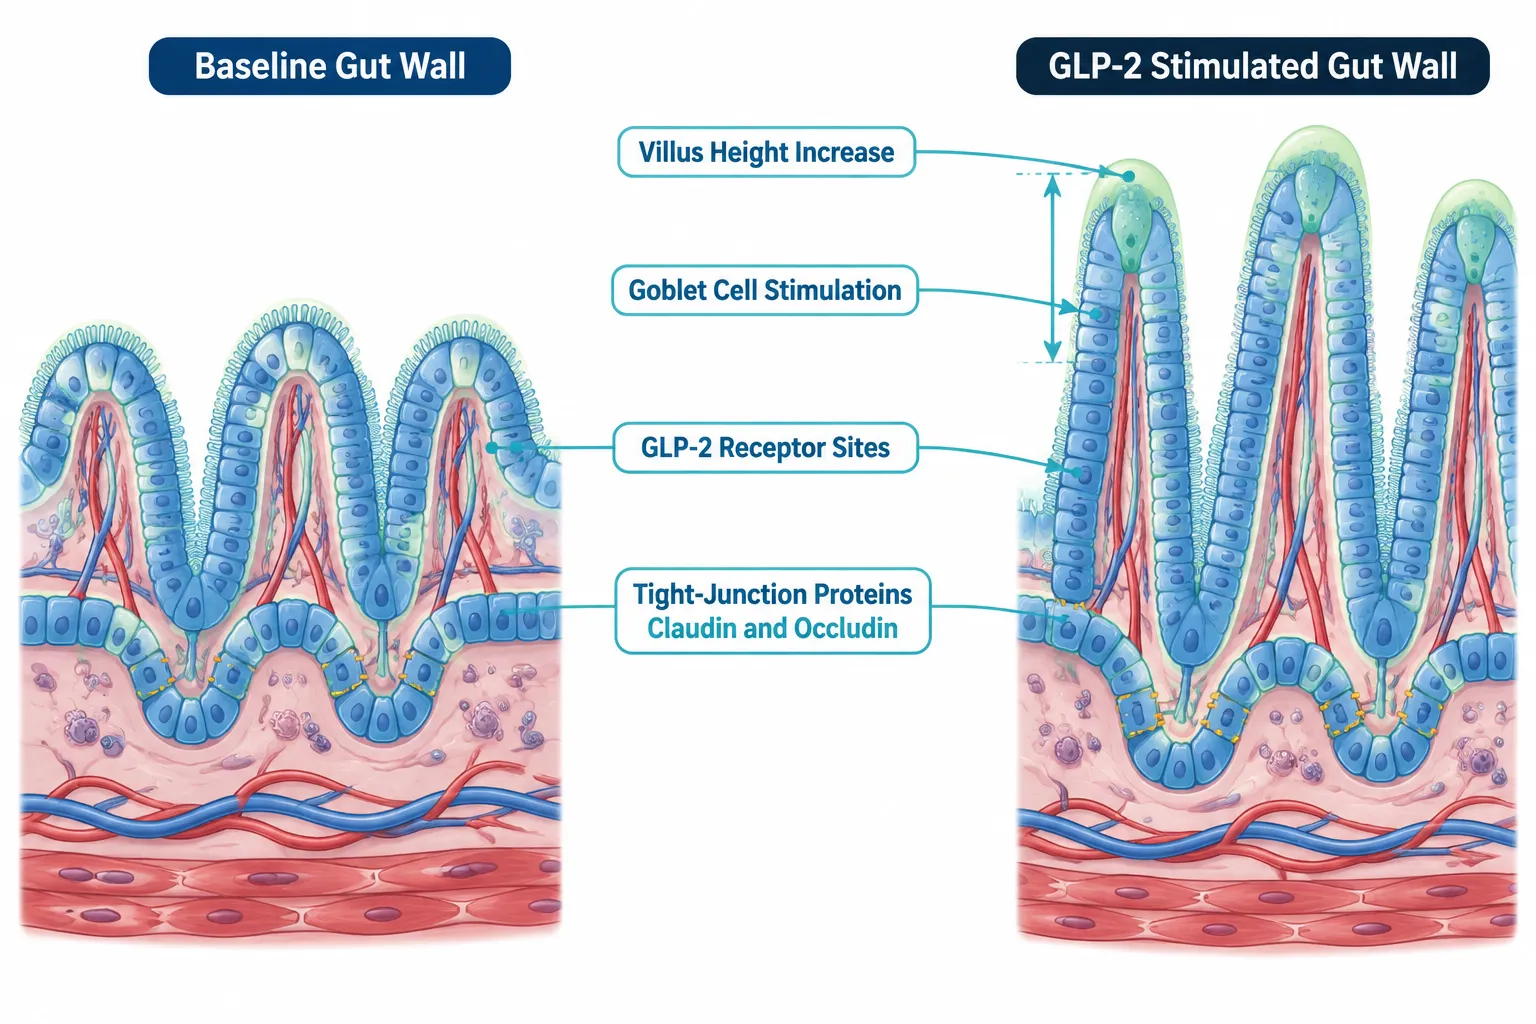
GLP-2 is co-secreted with GLP-1 from the same intestinal L-cells, but it acts on a completely separate receptor (GLP-2R) with no meaningful overlap in function. Its primary actions are:

  • Intestinal epithelial growth, stimulating mucosal repair and villus elongation
  • Nutrient absorption enhancement, increasing gut surface area
  • Reduced intestinal permeability, supporting barrier integrity

GLP-2 agonists such as teduglutide are approved for short bowel syndrome, a condition where intestinal absorptive surface is critically reduced. Apraglutide is in late-stage development for similar indications. These are not weight-loss drugs. They do not activate GLP-1R, do not suppress appetite centrally, and are not interchangeable with incretin therapies. Placing GLP-2 agonists in the same category as semaglutide or retatrutide reflects a fundamental mechanistic misunderstanding.

For those interested in the gut-focused metabolic research space, tesa peptide benefits and the broader where to buy tesa online resource offer adjacent context on peptides that influence metabolic tissue.

GLP-3: Conceptual Label, Not an Established Class

"GLP-3" appears in product marketing and some preliminary literature, but it does not currently represent a validated receptor class with confirmed pharmacology. The peptide fragment sometimes labeled GLP-3 is a further processing product of proglucagon, but no confirmed GLP-3 receptor has been characterized with reproducible, peer-reviewed receptor binding data.

"GLP-3 as a drug target remains conceptual. Researchers should treat any product marketed under this label with significant skepticism until receptor confirmation and clinical data exist."

This is a critical distinction in the broader discussion of GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically. Mixing a well-validated drug class with a label that lacks receptor confirmation creates confusion that can mislead both researchers and consumers.

For those exploring GLP-3-related research compounds, the GLP-3R 30mg peptide GA9 and GLP-3 Reta 30mg for sale listings provide research-grade options, while GLP3 where to buy resources offer sourcing guidance for laboratory investigation contexts.

Regulatory Status and the Research Peptide Distinction

Regulatory Status and the Research Peptide Distinction

The regulatory gap between approved GLP-1 receptor agonists and research peptides is substantial and consequential.

Approved GLP-1 RAs:

  • Manufactured under GMP (Good Manufacturing Practice) standards
  • Carry defined pharmacokinetic and safety profiles from large-scale trials
  • Prescribed by licensed clinicians for specific indications
  • Subject to post-market surveillance

Research peptides (including investigational GLP-related compounds):

  • Intended for laboratory and preclinical research use only
  • Not approved for human therapeutic use outside clinical trials
  • Purity and characterization depend entirely on supplier quality
  • Regulatory oversight varies significantly by jurisdiction

Retatrutide occupies a middle position: it is investigational, not approved, but it is studied under strict IND (Investigational New Drug) frameworks with rigorous safety monitoring, a very different context from informal research peptide use.

The safety profile of retatrutide in Phase 2 and early Phase 3 data mirrors the GLP-1 class in its most common adverse events: nausea, vomiting, and gastrointestinal discomfort, predominantly dose-dependent and transient. No novel safety signals have emerged that are categorically distinct from the established GLP-1 agonist class, though the glucagon agonism component warrants continued monitoring for effects on bone density and hepatic function.

For researchers sourcing lab tested peptides and evaluating supplier quality, purity documentation is non-negotiable. The visceral fat research tag provides additional context on metabolic endpoints relevant to GLP-related compound investigation.

Conclusion

The landscape of GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically is not as complicated as the terminology suggests, but it does require precision. Three actionable principles apply:

  1. Distinguish by receptor and regulatory status. GLP-1 RAs are approved, single-receptor drugs. Retatrutide is a triple agonist in Phase 3 development. GLP-2 agonists address gut integrity, not obesity. GLP-3 lacks confirmed receptor biology.

  2. Evaluate mechanistic claims critically. Any compound marketed as a "GLP-3 agonist" without peer-reviewed receptor confirmation deserves scrutiny. Receptor identity is the foundation of pharmacological classification.

  3. Apply the research-peptide standard. For laboratory investigation, source purity-verified, lab-tested compounds from documented suppliers. Never conflate research use with clinical therapy.

As Phase 3 retatrutide data matures through 2026 and beyond, the gap between triple agonism and standard GLP-1 monotherapy will become clearer. Staying grounded in mechanism, not marketing, is the most reliable guide through this rapidly evolving field.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/glp-1-receptor-agonists-vs-research-peptides-where-retatrutide-glp-3-and-glp-2-f.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:07:022026-09-14 13:07:02GLP-1 Receptor Agonists vs Research Peptides: Where Retatrutide, GLP-3, and GLP-2 Fit Mechanistically
Peptide Drug Interactions: How Research Peptides Interact With Common Medications

Peptide Drug Interactions: How Research Peptides Interact With Common Medications

September 14, 2026/0 Comments/in Uncategorized/by

Fewer than 20% of research peptides currently in active laboratory use have been formally evaluated for drug-drug interactions, a gap that carries real consequences as these compounds move closer to clinical and wellness applications. Understanding Peptide Drug Interactions: How Research Peptides Interact With Common Medications is no longer a niche concern for pharmacologists alone. Researchers, clinicians, and informed consumers need a clear, evidence-informed framework for thinking about these risks in 2026.

Key Takeaways

  • Most research peptides have limited CYP enzyme involvement, but this does not mean they are interaction-free.
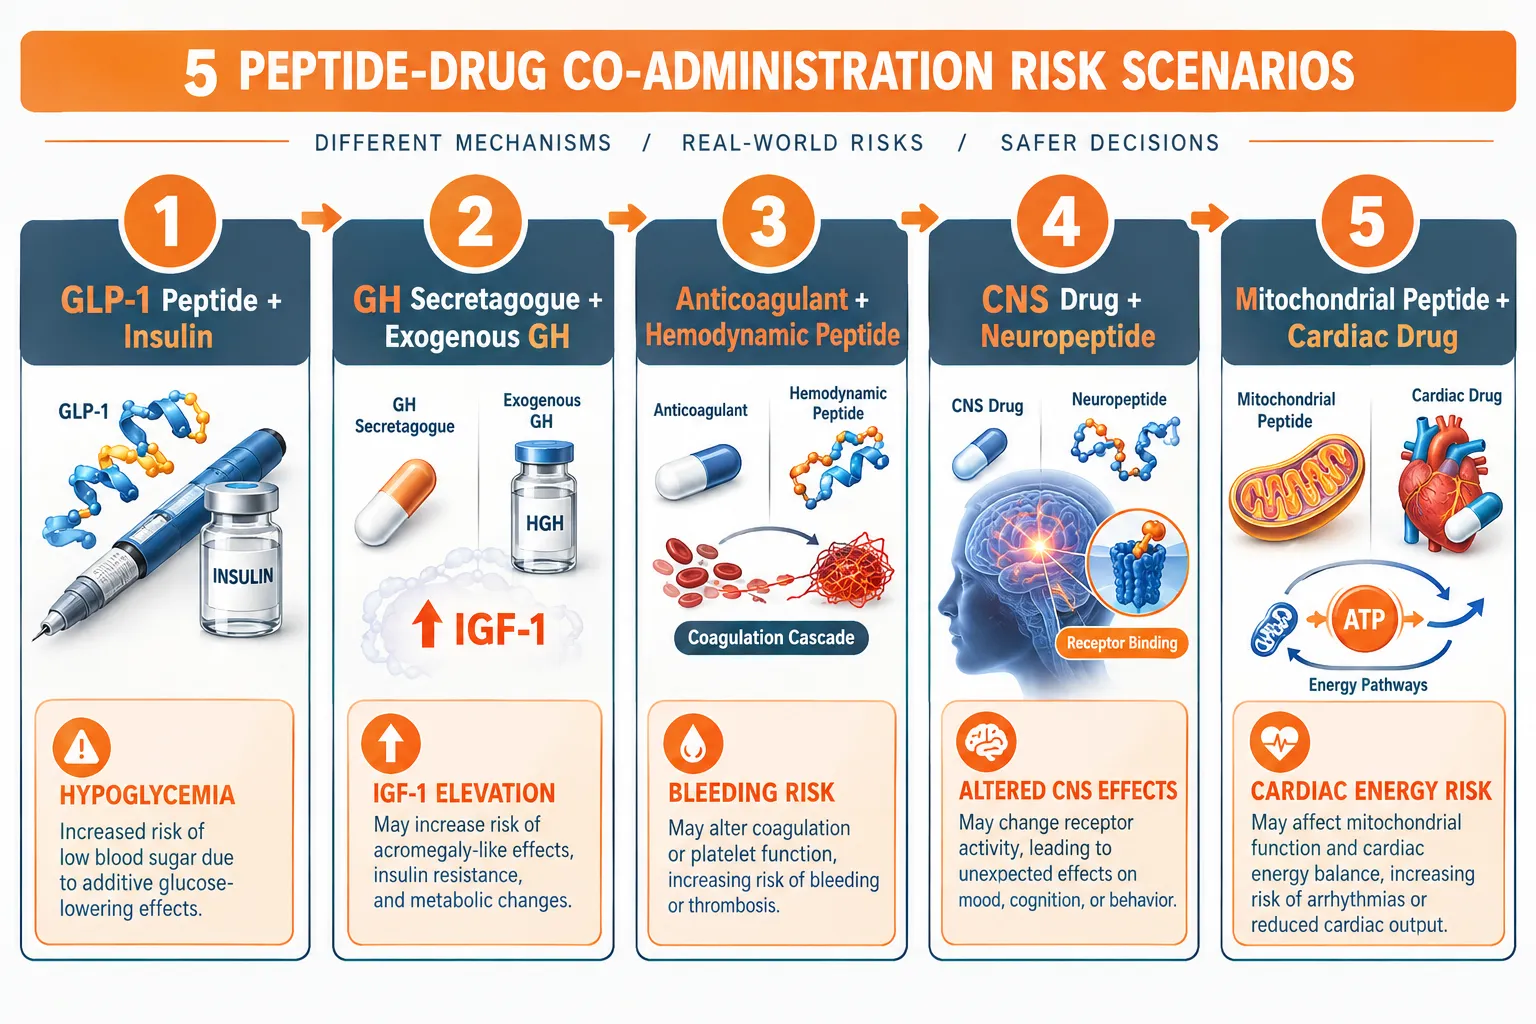
  • GLP-1 type peptides and growth hormone secretagogues carry the highest real-world interaction risk, particularly with insulin and antidiabetic drugs.
  • Peptide size, structural motifs, and route of administration all influence interaction potential.
  • Formal regulatory guidance on peptide drug interactions remains incomplete as of mid-2026.
  • Researchers and clinicians should apply a precautionary framework, especially in patients on anticoagulants, cardiovascular drugs, or CNS medications.

Why Peptide Drug Interactions Are Poorly Understood

Why Peptide Drug Interactions Are Poorly Understood

The science of peptide pharmacokinetics has advanced rapidly, but the field of peptide-drug interactions has not kept pace. A 2025 clinical review confirmed that formal guidance on this topic is still largely absent, leaving researchers to extrapolate from limited mechanistic data.

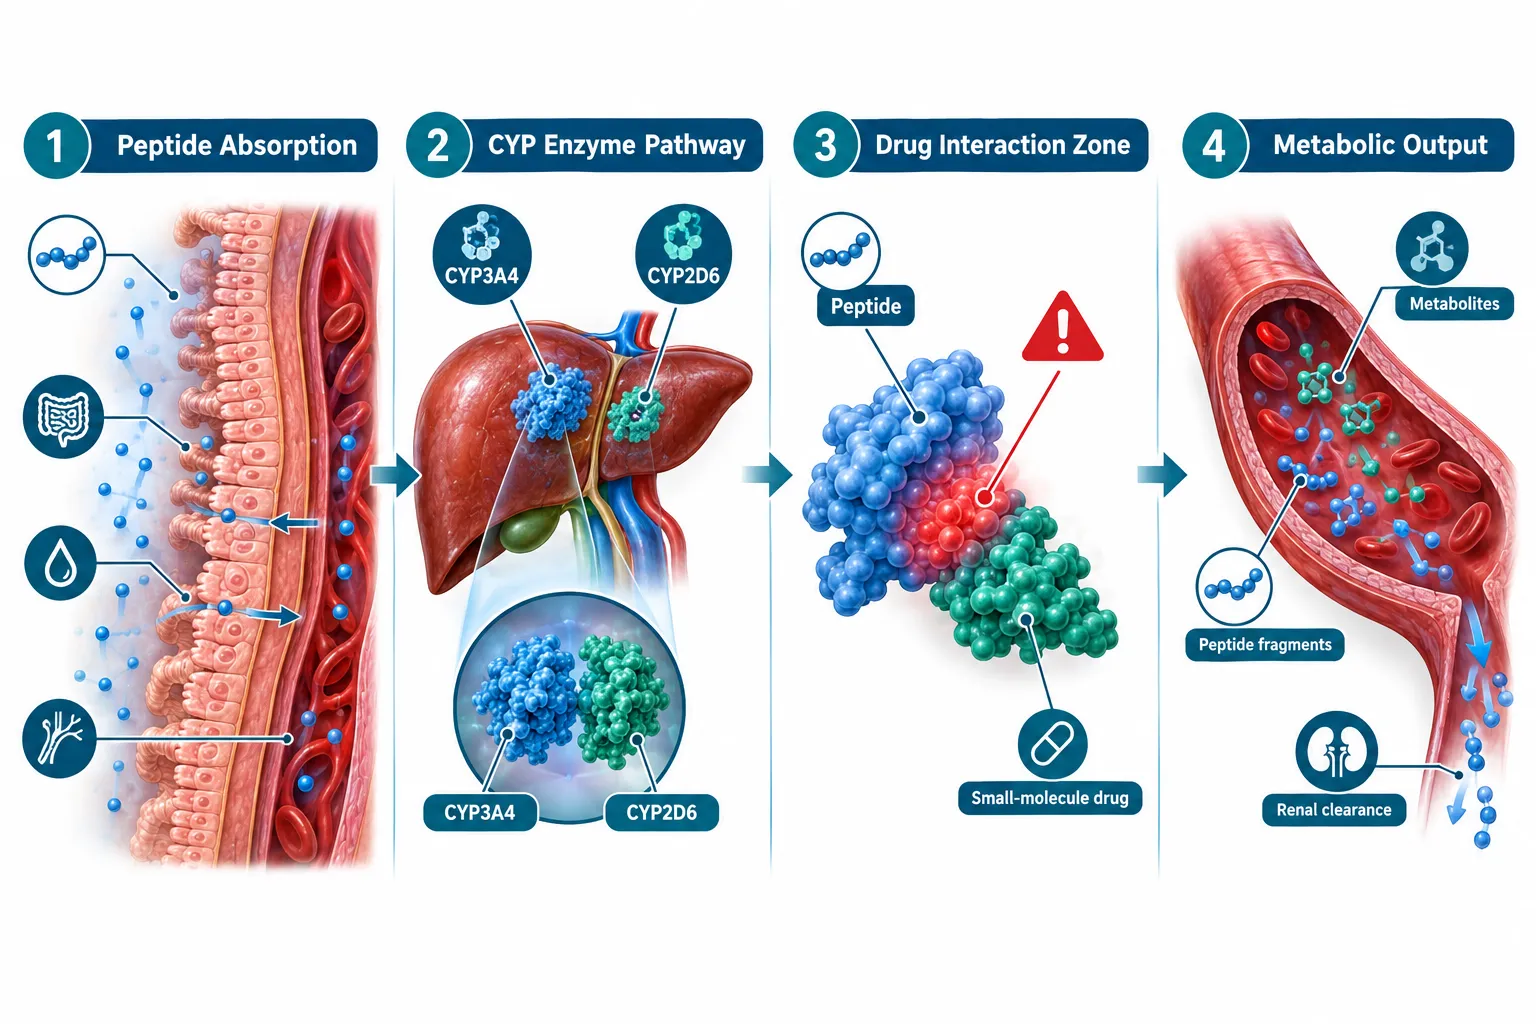
One reason for the knowledge gap is structural. Unlike small-molecule drugs, most peptides are broken down by proteases rather than by cytochrome P450 (CYP) liver enzymes. This means the classic drug interaction framework, built around CYP3A4, CYP2D6, and related pathways, does not map cleanly onto peptide pharmacology.

However, minimal CYP involvement is not the same as zero interaction risk. Peptides can still alter drug behavior through:

  • Receptor-level competition or synergy
  • Hormonal and metabolic downstream effects
  • Changes in gastric emptying, fluid balance, or hemodynamics
  • Indirect modulation of enzyme expression over time

A humanized mouse model published in 2025 confirmed low CYP-mediated drug-drug interaction (DDI) risk for larger peptides, and a 2024-2025 pharmacological interaction matrix analysis found that risk correlates with peptide size and the presence of non-peptide motifs. Smaller peptides with synthetic or hybrid structures carry meaningfully higher interaction potential.

For researchers exploring polypeptide peptides in cardiometabolic models, understanding this distinction is foundational.

"The absence of CYP involvement creates a false sense of safety. The real interaction risks for research peptides lie elsewhere, in hormonal cascades, receptor overlap, and hemodynamic shifts."

Peptide Drug Interactions: How Research Peptides Interact With Common Medications in Practice

Peptide Drug Interactions: How Research Peptides Interact With Common Medications in Practice

The most clinically significant interaction scenarios involve four major drug categories. Each presents a distinct mechanism and risk profile.

Insulin and Antidiabetic Drugs

GLP-1 peptides and growth hormone secretagogues can substantially amplify the glucose-lowering effects of insulin, metformin, and sulfonylureas. Co-administration creates a compounding hypoglycemia risk that is not always predictable from either agent alone. This is one of the best-documented interaction categories in the research peptide space.

Growth Hormone and IGF-1 Pathways

Peptides that stimulate endogenous growth hormone release, including several widely studied secretagogues, should generally not be combined with exogenous growth hormone. The additive effect on IGF-1 elevation carries metabolic and cardiovascular consequences. This combination is broadly flagged as one to avoid in research protocols.

For context on how one mitochondrial-targeted peptide is evaluated in isolation, see SS-31 10mg research peptide considerations.

Anticoagulants and Cardiovascular Medications

Even when CYP pathways are uninvolved, peptides that alter hemodynamics, endothelial function, or fluid balance can change the effective exposure of anticoagulants like warfarin or direct oral anticoagulants (DOACs). This is a pharmacodynamic interaction rather than a pharmacokinetic one, and it is frequently overlooked.

Interaction Risk Summary by Drug Class

Drug Class Interaction Type Risk Level
Insulin / Antidiabetics Pharmacodynamic (additive) High
Exogenous Growth Hormone Hormonal cascade (additive) High
Anticoagulants / CVD drugs Hemodynamic / fluid balance Moderate-High
CNS Medications Receptor-level overlap Moderate (context-dependent)

CNS and Neurological Drugs

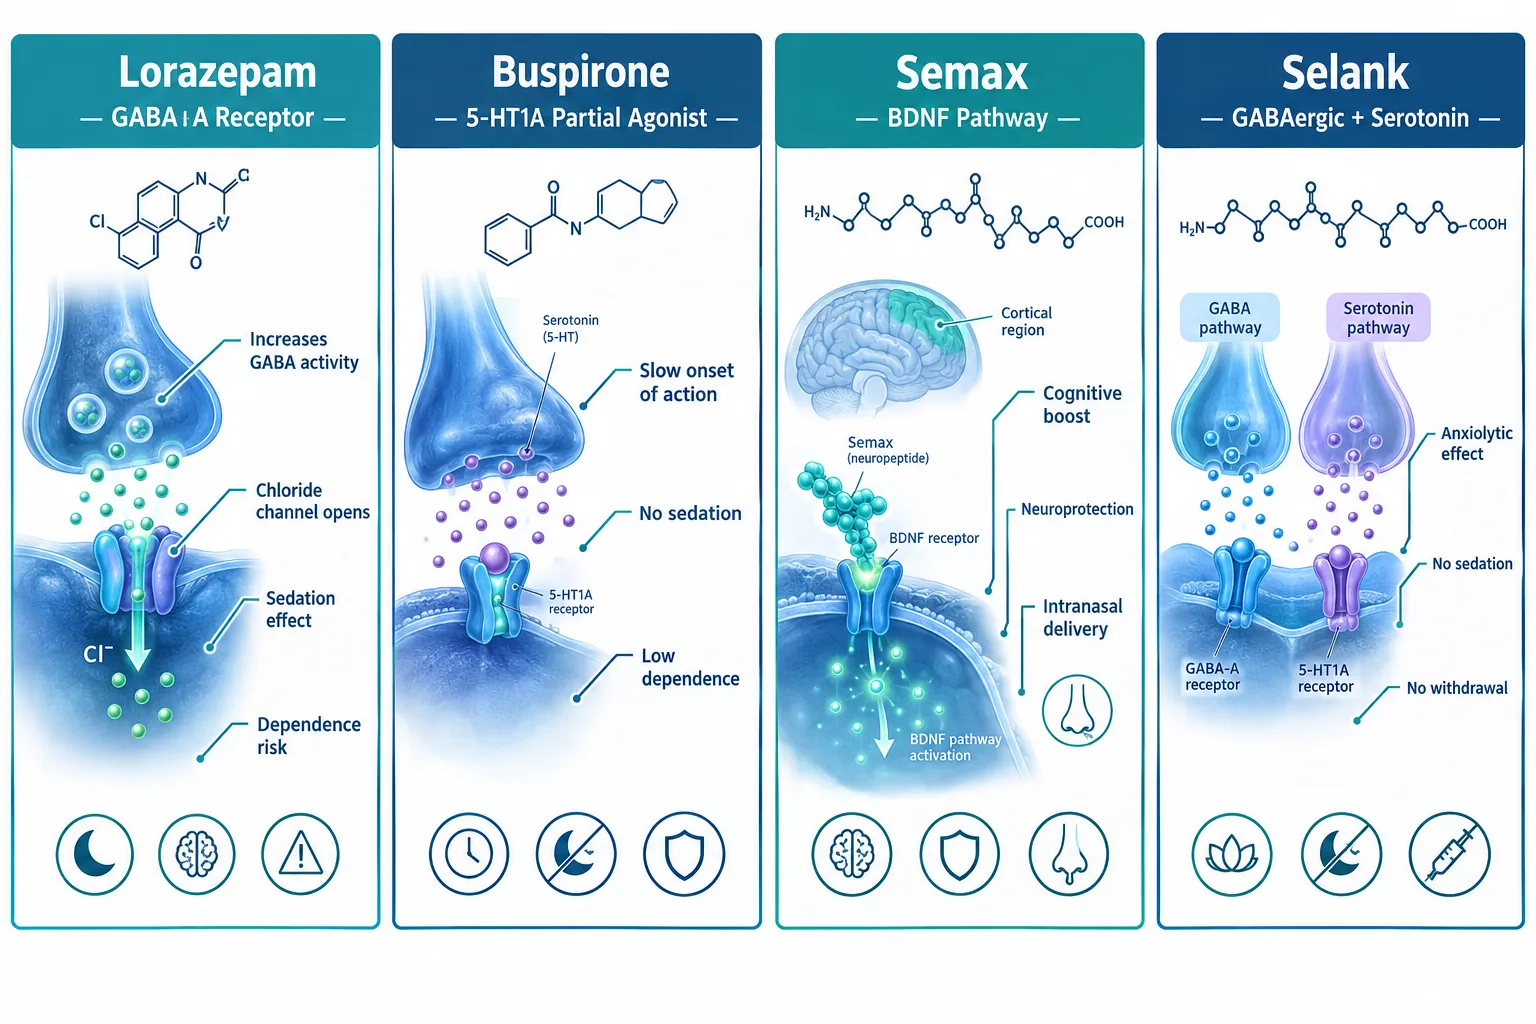
Neuropeptides and peptides with CNS activity, including some under active Semax research protocols, may interact with antidepressants, anxiolytics, or antiepileptics through receptor-level mechanisms. The interaction data here is sparse, and safety advocacy groups flagged in June 2026 that interaction risk for wellness and "PCAC" peptides remains largely unknown.

Regulatory Context and What It Means for Researchers

Regulatory Context and What It Means for Researchers

The regulatory landscape shifted meaningfully in the first half of 2026. In March and April 2026, the FDA took enforcement action against sellers of "research-use-only" GLP-1 analog peptides, signaling a harder line on compounds that blur the boundary between research chemicals and unapproved therapeutics. Then, in July 2026, a regulatory framework update confirmed that while CYP involvement for most peptides remains minimal, caution is warranted in high-risk patient populations.

On July 28, 2026, the FDA also shifted its scientific position on generic peptide products, a move with downstream implications for how interaction data will be required and evaluated going forward.

For researchers sourcing compounds, working with lab tested peptides that carry documented purity profiles is a baseline requirement. Impurities and degradation products can introduce interaction variables that are entirely separate from the peptide's intended pharmacology.

Researchers studying endocrine-active compounds should also review how peptides interface with receptor biology, as covered in the analysis of peptides and polypeptides in endocrine pharmacology.

Practical precautions for 2026 research contexts:

  • Document all co-administered agents before initiating any peptide protocol
  • Apply heightened scrutiny when subjects are on insulin, anticoagulants, or cardiovascular drugs
  • Treat absence of CYP data as absence of evidence, not evidence of absence
  • Monitor for pharmacodynamic interactions even when pharmacokinetic data is reassuring
  • Consult updated FDA guidance before working with GLP-1 class analogs

Conclusion

Peptide Drug Interactions: How Research Peptides Interact With Common Medications represent a genuine and underappreciated safety domain. The low CYP involvement of most peptides does not eliminate interaction risk, it simply shifts where that risk lives. The highest-priority concerns in 2026 involve GLP-1 and growth hormone-related peptides combined with insulin or exogenous GH, anticoagulants in patients with hemodynamic-active peptides, and CNS drugs paired with neuropeptides.

Actionable next steps for researchers and practitioners:

  1. Build a complete co-medication profile before any peptide protocol begins.
  2. Prioritize compounds with documented purity and available pharmacological data.
  3. Monitor the FDA's evolving position on peptide classification, particularly for GLP-1 analogs.
  4. Apply pharmacodynamic interaction logic even when pharmacokinetic data is absent.
  5. Revisit interaction assumptions regularly, the evidence base is moving fast in 2026.

The field is advancing. Staying ahead of the interaction risk curve is not optional, it is foundational to responsible research practice.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptide-drug-interactions-how-research-peptides-interact-with-common-medications-1.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:06:172026-09-14 13:06:17Peptide Drug Interactions: How Research Peptides Interact With Common Medications
Retatrutide 2026 Phase 3 Results: What the Latest Trial Data Means for GLP-3 Research

Retatrutide 2026 Phase 3 Results: What the Latest Trial Data Means for GLP-3 Research

September 14, 2026/0 Comments/in Uncategorized/by

Obesity affects more than one billion people worldwide, yet until recently, pharmacologic treatments rarely achieved weight loss beyond 15 to 20 percent of body weight. The Retatrutide 2026 Phase 3 Results have changed that benchmark entirely, producing efficacy numbers that researchers once associated only with bariatric surgery. Understanding what this data means for GLP-3 and triple-agonist science is now one of the most pressing questions in metabolic medicine.

Key Takeaways

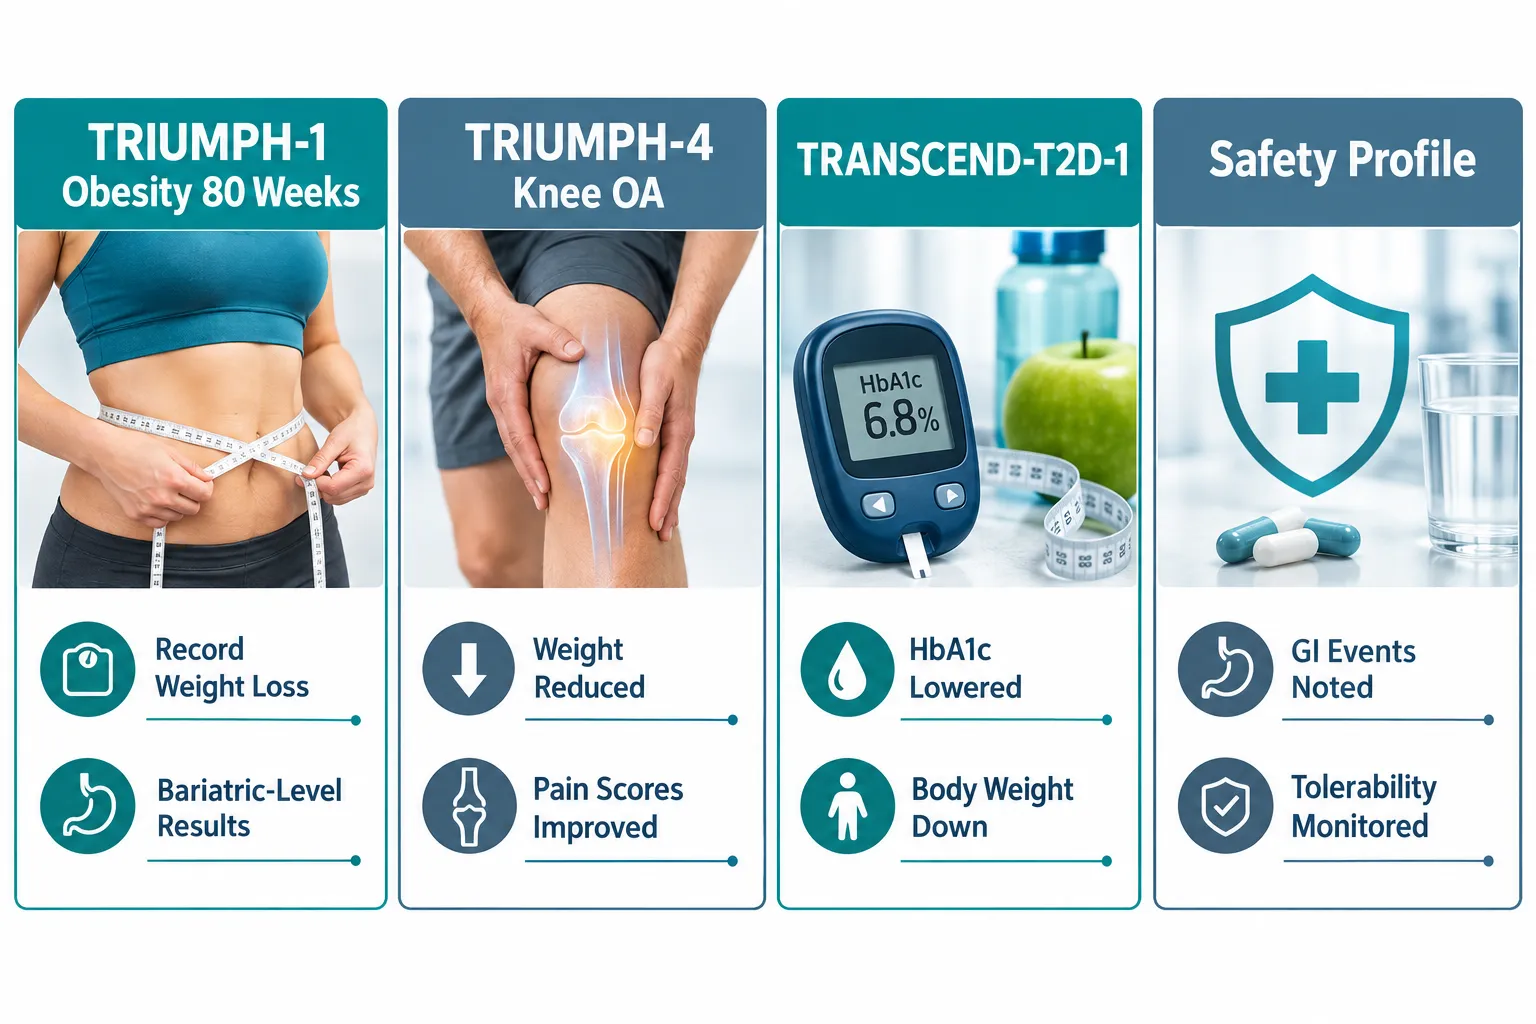
  • Retatrutide's TRIUMPH-1 trial delivered unprecedented weight loss over 80 weeks, surpassing all prior pharmacologic benchmarks.
  • Phase 3 data now spans obesity, type 2 diabetes, and musculoskeletal comorbidities, broadening the clinical picture significantly.
  • Triple-receptor activation, targeting GLP-1, GIP, and glucagon receptors simultaneously, has been validated at scale for the first time.
  • A meaningful adverse-event profile, particularly gastrointestinal, requires careful interpretation alongside the efficacy headlines.
  • Regulatory decisions in 2026 remain optimistic but are not guaranteed; the commercialization path is still unfolding.

How Retatrutide Works: The Triple-Agonist Mechanism

Retatrutide is a once-weekly injectable peptide that simultaneously activates three receptors: glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon. This triple-agonist profile distinguishes it from earlier agents like semaglutide (GLP-1 only) or tirzepatide (GLP-1 and GIP). By adding glucagon receptor activation, retatrutide boosts energy expenditure in addition to suppressing appetite and improving insulin sensitivity.

How Retatrutide Works: The Triple-Agonist Mechanism

This multi-receptor strategy is the conceptual foundation of what researchers now call GLP-3 pharmacology, a term used informally to describe agents that go beyond the dual-agonist class. The Retatrutide 2026 Phase 3 Results represent the first large-scale human validation of this mechanism, moving it from Phase 2 hypothesis to Phase 3 proof.

Researchers interested in related peptide mechanisms can explore GLP-3 Reta 30mg research materials and Reta 10mg research resources for additional context on dosing formats studied in this class.

Breaking Down the TRIUMPH and TRANSCEND Phase 3 Trials

The Phase 3 program for retatrutide is structured across multiple trials, each targeting a distinct population or comorbidity profile.

TRIUMPH-1: The Headline Obesity Trial

TRIUMPH-1 enrolled adults with obesity over an 80-week period, a notably longer horizon than most prior obesity trials. The results produced weight loss figures that crossed into what clinicians describe as "bariatric-level" territory, meaning reductions comparable to surgical interventions. This single data point has reshaped the ceiling for what pharmacologic treatment can achieve.

TRIUMPH-2 and TRIUMPH-3: Broadening the Evidence Base

These trials extended the obesity evidence across participants with varying comorbidities, including cardiovascular risk factors and metabolic syndrome. The consistency of weight loss outcomes across these populations strengthened the argument that retatrutide's efficacy is not limited to a narrow patient profile.

TRIUMPH-4: Weight Loss Meets Joint Health

TRIUMPH-4 is particularly notable. It enrolled patients with both obesity and knee osteoarthritis, a population where weight reduction directly correlates with pain relief and functional improvement. The dual benefit, meaningful weight loss alongside measurable reductions in pain scores, positions retatrutide as a potential disease-modifying agent for musculoskeletal conditions driven by excess weight.

TRANSCEND-T2D-1: Glycemic Efficacy in Type 2 Diabetes

The TRANSCEND-T2D-1 trial addressed type 2 diabetes specifically. Phase 3 data confirmed significant HbA1c reductions alongside substantial body weight loss, reinforcing that the glucagon receptor component does not compromise glycemic control, a concern raised in earlier mechanistic discussions.

TRANSCEND-T2D-1: Glycemic Efficacy in Type 2 Diabetes

“The TRIUMPH-1 data effectively moved the goalposts for what obesity medicine can accomplish without surgery. That is not a small claim, it is a structural shift in the field.”

For researchers examining how stacked peptide protocols compare, the IPA Sermorelin Stack Research page offers relevant context on multi-peptide research design.

Safety Profile, Industry Reaction, and What Comes Next

Adverse Events: The Full Picture

No Phase 3 dataset is complete without a serious look at tolerability. Retatrutide's adverse-event profile is dominated by gastrointestinal effects, nausea, vomiting, and diarrhea, consistent with the GLP-1 class broadly. However, the glucagon component introduces additional considerations around heart rate elevation and potential lean mass effects that researchers are monitoring closely. Efficacy is compelling, but it does not erase these signals.

Trial Primary Population Key Outcome Notable Safety Signal
TRIUMPH-1 Obesity (80 weeks) Bariatric-level weight loss GI events, heart rate
TRIUMPH-4 Obesity + knee OA Weight loss + pain reduction Consistent with class
TRANSCEND-T2D-1 Type 2 diabetes HbA1c reduction + weight loss GI tolerability

Expert and Industry Reaction in 2026

The metabolic research community has responded with measured enthusiasm. The consensus is that retatrutide establishes a new pharmacologic ceiling, but experts are careful to note that long-term cardiovascular outcome data, the kind that defines regulatory and prescribing confidence, is still maturing. Industry analysts in 2026 view a regulatory filing as imminent but not guaranteed to move quickly through review.

Implications for GLP-3 Research

The Retatrutide 2026 Phase 3 Results validate the core premise of triple-agonist research: that adding glucagon receptor activation to a GLP-1/GIP backbone produces meaningfully superior outcomes. This has accelerated interest in the broader GLP-3 research space and is driving investment into next-generation molecules that may refine the receptor balance further.

Researchers exploring this compound can review available Reta 20mg for sale and GLP3 Reta CAG 10mg for sale research formats, as well as the buy Reta peptide resource page for procurement information relevant to preclinical study contexts.

For those studying complementary mitochondrial and metabolic pathways, the SS-31 mitochondrial research themes resource provides useful mechanistic background on energy metabolism at the cellular level.

Implications for GLP-3 Research

Unanswered Questions

Several critical gaps remain:

  • Long-term cardiovascular outcomes: No dedicated CVOT data has been published for retatrutide yet.
  • Lean mass preservation: Whether the weight lost is predominantly fat or includes significant muscle loss requires further characterization.
  • Durability after discontinuation: Weight regain patterns post-treatment remain under study.
  • Optimal dosing architecture: The Phase 3 program used specific titration schedules; real-world dosing flexibility is untested.

Conclusion

The Retatrutide 2026 Phase 3 Results represent a genuine inflection point in metabolic pharmacology. TRIUMPH-1's bariatric-level weight loss, TRIUMPH-4's dual benefit in osteoarthritis, and TRANSCEND-T2D-1's glycemic efficacy together confirm that triple-receptor activation is not a theoretical advantage, it is a measurable clinical reality.

Actionable next steps for researchers and clinicians:

  • Monitor regulatory agency communications closely, as a filing decision is expected within the current review cycle.
  • Prioritize review of the full safety dataset, not just the efficacy headlines, before drawing clinical conclusions.
  • Track lean mass and cardiovascular outcome sub-analyses as they are published from the TRIUMPH program.
  • Engage with the GLP-3 research literature now, as the field is moving rapidly and foundational papers are accumulating.
  • Consider how comorbidity-specific trial designs, like TRIUMPH-4, may inform future research protocols in musculoskeletal and metabolic overlap conditions.

Retatrutide has set a new standard. The research community's task now is to understand exactly what that standard costs, who benefits most, and how to build on it responsibly.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-2026-phase-3-results-what-the-latest-trial-data-means-for-glp-3-rese.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:06:002026-09-14 13:06:00Retatrutide 2026 Phase 3 Results: What the Latest Trial Data Means for GLP-3 Research
Peptide Research and Omeprazole: What Acid-Suppressing Drugs Mean for GLP-2 and Gut-Focused Studies

Peptide Research and Omeprazole: What Acid-Suppressing Drugs Mean for GLP-2 and Gut-Focused Studies

September 14, 2026/0 Comments/in Uncategorized/by

More than 15 percent of adults in Western countries take a proton pump inhibitor (PPI) like omeprazole on a regular basis, yet this common medication rarely appears as a controlled variable in gut-focused peptide trials. That gap matters more than most researchers realize. Understanding peptide research and omeprazole interactions, especially what acid-suppressing drugs mean for GLP-2 and gut-focused studies, is quickly becoming a prerequisite for designing credible intestinal peptide protocols in 2026.

Key Takeaways

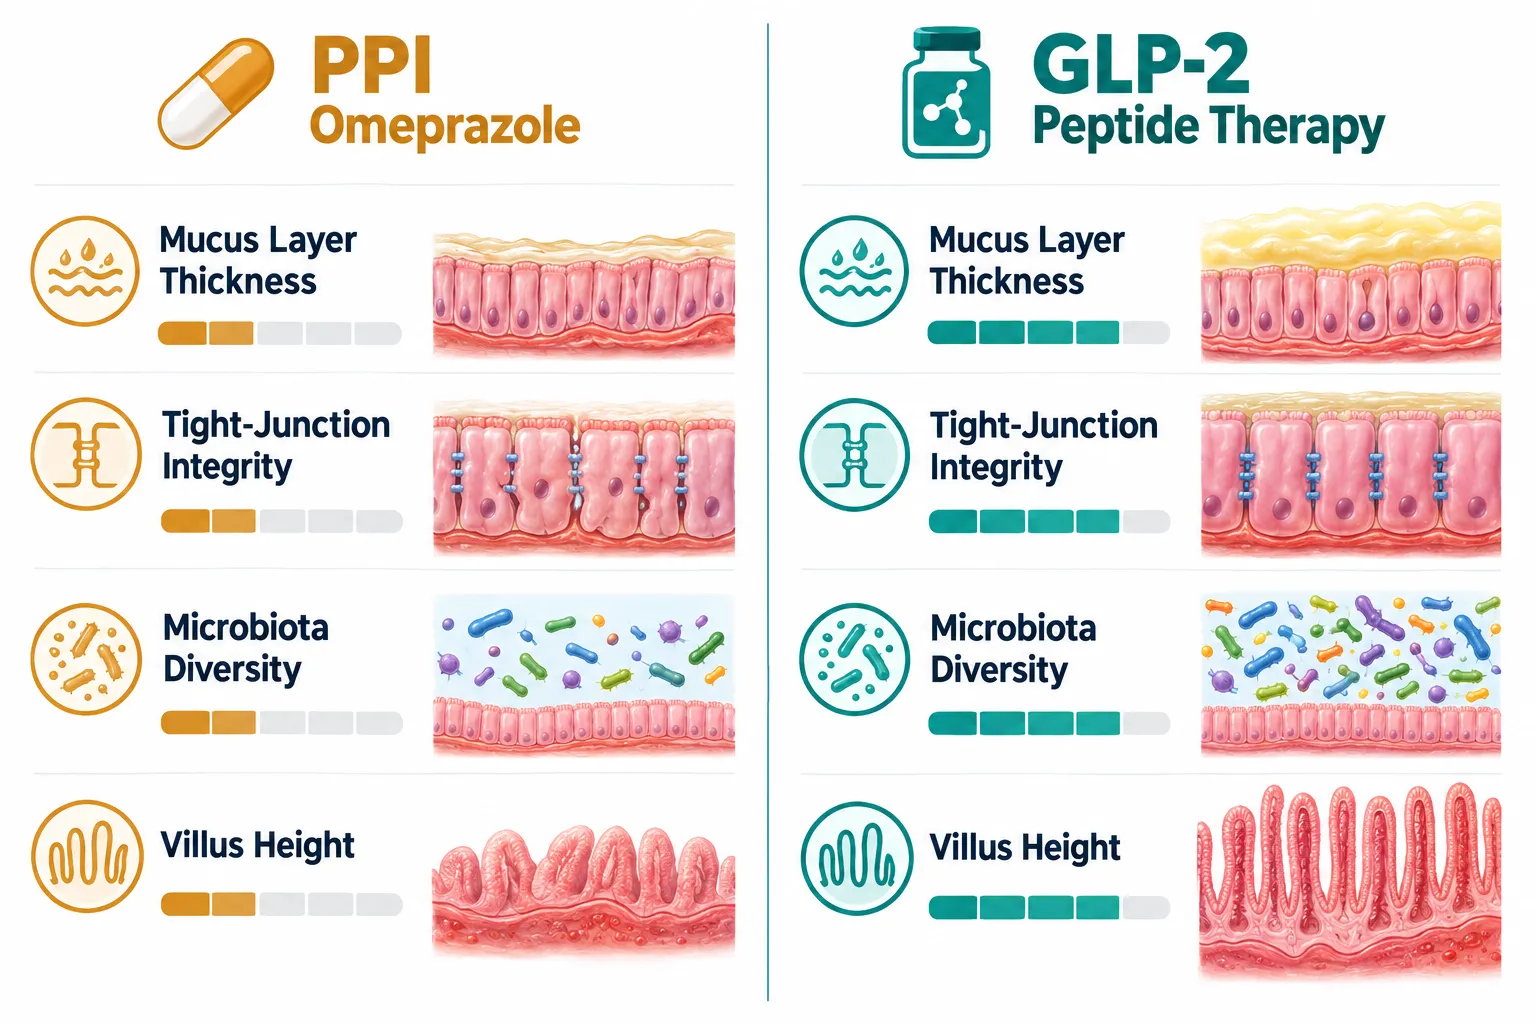
  • Omeprazole and other PPIs modestly improve gut barrier function, but GLP-2 peptides produce significantly larger gains in villus height and tight-junction integrity through distinct downstream mechanisms.
  • Pharmacokinetic data show omeprazole does not meaningfully blunt GLP-peptide exposure; any increase in drug absorption is small and clinically irrelevant.
  • Long-term PPI use reduces gut microbiota diversity, while GLP-2 therapy is linked to more favorable microbiota profiles, making PPI status a critical covariate in intestinal studies.
  • Oral peptide formulations should follow an empty-stomach dosing window, with PPI administration delayed by at least 30 minutes to protect bioavailability.
  • Future GLP-2 and teduglutide trials are expected to treat chronic PPI use as a pre-specified variable or exclusion criterion to isolate peptide-driven mucosal effects.

How Omeprazole Affects the Gut Environment Relevant to Peptide Research

How Omeprazole Affects the Gut Environment Relevant to Peptide Research

Omeprazole works by irreversibly blocking the hydrogen-potassium ATPase enzyme in gastric parietal cells, suppressing acid output and raising gastric pH. That pH shift creates downstream changes throughout the gastrointestinal tract, changes that overlap with the very endpoints gut-focused peptide studies are designed to measure.

What PPIs do to the gut environment:

  • Modestly increase mucus layer thickness
  • Improve tight-junction integrity by reducing acid-driven mucosal injury
  • Raise gastric pH, which can affect the absorption window for orally administered compounds
  • With long-term use, reduce gut microbiota diversity, a recognized risk in chronic PPI therapy
  • Associate with a small but statistically significant increase in gastric cancer risk over 10 years (number needed to harm approximately 1,191 over a decade)

PPIs also carry documented risks including infection susceptibility and nutrient malabsorption. These effects are not trivial in a research context. When a participant is taking omeprazole daily, the baseline gut environment is already shifted, and that shift can confound mucosal endpoints in any gut-focused peptide study.

Key point: PPIs and GLP-2 peptides act on overlapping but not identical gut endpoints. Failing to account for PPI use in study design risks attributing PPI-driven changes to the peptide under investigation.

GLP-2 Mechanisms Compared to Acid Suppression

GLP-2 Mechanisms Compared to Acid Suppression

GLP-2 (glucagon-like peptide-2) and its clinical analog teduglutide (GLP-2-T) operate through mechanisms that are fundamentally different from acid suppression. Understanding this distinction is central to interpreting peptide research and omeprazole co-administration scenarios.

How GLP-2 remodels the intestinal mucosa:

  • Directly stimulates goblet cells to increase mucus production
  • Upregulates tight-junction proteins claudin and occludin, strengthening the epithelial barrier
  • Promotes enterocyte proliferation, producing measurable increases in villus height
  • Supports crypt cell survival and reduces apoptosis along the intestinal lining

Compared to the modest barrier improvements seen with PPIs, GLP-2 and GLP-2-T produce substantially larger gains in villus height and barrier function. Longitudinal data from 2025 link GLP-2-T therapy to improved barrier integrity and more favorable microbiota profiles, a meaningful contrast to the microbiota diversity losses associated with long-term PPI use.

For researchers exploring GLP-3 peptide variants and related proglucagon-derived compounds, this mechanistic separation is equally relevant. The mucosal effects of GLP-class peptides operate sufficiently downstream of acid secretion that elevated gastric pH from omeprazole does not appear to blunt their activity.

Those working with GLP-3 R peptide formulations should note that the structural similarities across proglucagon-derived peptides make these pharmacokinetic findings broadly applicable to the class.

Pharmacokinetics: Does Omeprazole Interfere With GLP-Peptide Absorption?

This is the practical question most researchers and clinicians ask first. The short answer, supported by pharmacokinetic data, is no, not in any clinically meaningful way.

Randomized pharmacokinetic studies using oral semaglutide as a structural proxy for proglucagon-derived peptides found only a small, non-statistically-significant increase in peptide exposure when omeprazole was co-administered. The AUC ratio was approximately 1.13 and the Cmax ratio approximately 1.16, changes deemed clinically irrelevant, with no dose adjustment required.

Updated guidance for oral semaglutide in 2026 confirms it can be safely combined with omeprazole, with one practical caveat: take the peptide first on an empty stomach and delay omeprazole by at least 30 minutes. This timing protocol protects bioavailability without requiring formulation changes.

Similar findings apply across the GLP class:

Peptide/Drug Omeprazole Interaction Dose Adjustment Needed?
Oral semaglutide Minor AUC increase (~13%) No
Tirzepatide No known PK or PD interaction No
Liraglutide Low-severity rating, no signal No

For labs sourcing research-grade GLP-3 peptides for gut-focused protocols, this data supports including omeprazole-using participants without automatic exclusion, provided PPI status is recorded and stratified in the analysis.

Study Design Implications: Treating PPI Use as a Covariate

Study Design Implications: Treating PPI Use as a Covariate

The convergence of evidence in 2026 points toward a clear methodological standard for future GLP-2 and teduglutide trials: chronic PPI use must be treated as a pre-specified covariate or exclusion criterion.

The rationale is straightforward. PPIs independently affect:

  1. Mucus layer thickness
  2. Tight-junction protein expression
  3. Gut microbiota composition and diversity
  4. Gastric and intestinal cancer risk over time
  5. Glycemic markers, PPIs show modest HbA1c-lowering effects, likely via increased gastrin and downstream incretin activity

That last point is particularly relevant. Meta-analytic data through 2025-2026 suggest PPIs may modestly improve glycemic control in type 2 diabetes, with HbA1c reductions comparable to some incretin-based therapies. This creates a potential mild synergy, not antagonism, when PPIs are combined with GLP-1 receptor agonists or other gut-acting peptides.

For researchers also evaluating mitochondrial or systemic peptides alongside gut endpoints, resources such as the LL-37 versus SS-31 peptide comparison offer useful context on how peptide class affects study variable selection.

Labs sourcing lab-tested peptides for intestinal research should document participant PPI status at enrollment and consider stratified randomization by PPI use to prevent confounding at the analysis stage.

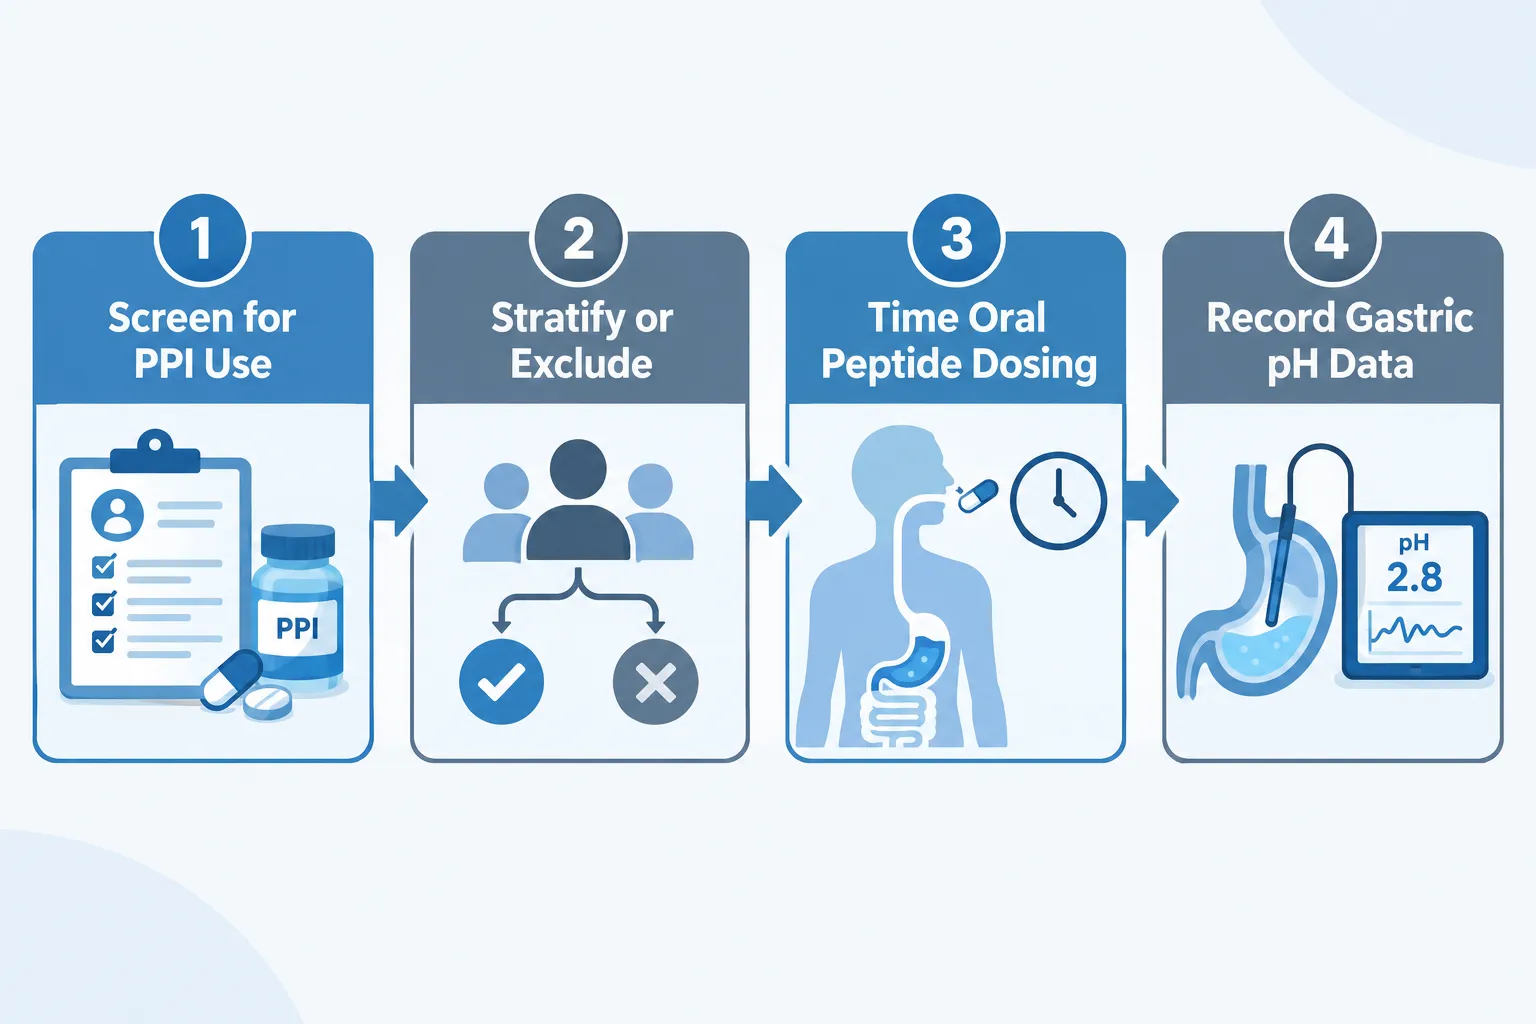
Recommended steps for GLP-2 trial design in 2026:

  1. Screen all participants for current PPI use at baseline
  2. Stratify or exclude chronic PPI users based on study endpoints
  3. For oral peptide arms, standardize the dosing window (empty stomach, 30-minute PPI delay)
  4. Record gastric pH data as a secondary variable where feasible
  5. Pre-specify PPI status as a covariate in the statistical analysis plan

As oral peptide formulations expand, following the template established by oral semaglutide, future GLP-2 analog trials are expected to mirror these protocols, optimizing dosing windows relative to PPIs while leveraging the finding that PPI-induced pH changes alone do not meaningfully suppress peptide exposure.

Conclusion

The relationship between peptide research and omeprazole is more nuanced than a simple drug interaction. Omeprazole does not meaningfully block GLP-2 or GLP-1 class peptide activity at the pharmacokinetic level, but it does independently alter the gut environment in ways that directly overlap with mucosal endpoints these peptides are designed to affect.

Actionable next steps for researchers and study designers:

  • Always document and stratify PPI use in gut-focused peptide protocols, do not treat it as background noise
  • Apply the 30-minute empty-stomach dosing rule for any oral peptide formulation when participants are on PPIs
  • Treat long-term PPI use as a potential confounder for microbiota, barrier integrity, and glycemic endpoints
  • Review updated 2026 guidance for oral GLP-class peptides before finalizing co-administration protocols
  • Consider pre-specifying PPI status as an exclusion criterion or stratification variable in GLP-2-T trials targeting villus height and tight-junction outcomes

Getting this variable right is not a minor methodological detail, it is the difference between clean data and results that cannot be replicated.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptide-research-and-omeprazole-what-acid-suppressing-drugs-mean-for-glp-2-and-g.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:05:452026-09-14 13:05:45Peptide Research and Omeprazole: What Acid-Suppressing Drugs Mean for GLP-2 and Gut-Focused Studies
Phosphate Buffered Saline for Peptide Reconstitution: A Complete Research Protocol Guide

Phosphate Buffered Saline for Peptide Reconstitution: A Complete Research Protocol Guide

September 14, 2026/0 Comments/in Uncategorized/by

Roughly 30% of peptide reconstitution failures in research settings trace back to a single, preventable error: choosing the wrong solvent. For researchers working with synthetic peptides, that choice starts with understanding when phosphate buffered saline is the right tool and when it is not. This guide to Phosphate Buffered Saline for Peptide Reconstitution: A Complete Research Protocol Guide covers everything a researcher needs to make that decision confidently, execute the protocol correctly, and store reconstituted stocks safely.

Key Takeaways

  • PBS at pH 7.4 closely mimics physiological conditions, making it ideal for hydrophilic and cell-compatible peptide assays.
  • Phosphate ions can catalyze deamidation and other degradation pathways in susceptible peptides, so PBS is not universally appropriate.
  • Proper concentration calculation, sterile filtration, and cold-chain storage are non-negotiable steps in any PBS reconstitution protocol.
  • Alternatives such as bacteriostatic water, HEPES-buffered saline, and dilute acetic acid each serve specific peptide chemistries better than PBS in certain cases.
  • Sourcing high-purity, third-party-tested peptides is the foundation of any reliable reconstitution outcome.

Why PBS Remains the Default Solvent in Peptide Research

Phosphate buffered saline is a water-based salt solution that maintains a stable pH of 7.4 while matching the osmolarity of human plasma at approximately 300 mOsm/kg. Those two properties explain its dominance in cell culture, biochemical assays, and in vivo research models.

Why PBS Remains the Default Solvent in Peptide Research

For hydrophilic peptides with a net neutral or slightly negative charge at physiological pH, PBS provides an aqueous environment that supports full dissolution without introducing organic solvents that could disrupt downstream cell viability. Researchers running Semax research protocols and similar neuropeptide studies frequently rely on PBS precisely because the buffer does not interfere with receptor-binding assays or neuronal cell lines.

When PBS is the right choice:

  • Hydrophilic peptides that dissolve readily in water
  • Cell-based assays requiring physiological osmolarity
  • In vivo models where isotonicity is critical
  • Short-term stocks used within 24 to 72 hours

When PBS should be avoided:

  • Peptides containing asparagine or glutamine residues prone to deamidation (phosphate accelerates this reaction)
  • Highly hydrophobic sequences that require DMSO or dilute organic acid as a primary solvent
  • Long-term frozen stocks where phosphate precipitation at low temperatures can alter effective concentration

"PBS is not a universal default. It is the best default for a defined subset of peptide chemistries."

Core Protocol Steps for Reconstituting Peptides in PBS

Following a standardized workflow reduces variability and protects peptide integrity from the moment the lyophilized powder is opened.

Core Protocol Steps for Reconstituting Peptides in PBS

Step 1: Assess Peptide Solubility Before Reconstitution

Review the manufacturer's certificate of analysis and any published solubility data. Peptides with a high proportion of hydrophobic residues (leucine, isoleucine, phenylalanine, valine) will likely require a co-solvent step before PBS dilution. Peptides with multiple charged residues at physiological pH are strong candidates for direct PBS dissolution.

Step 2: Prepare or Verify Sterile PBS

Use sterile, endotoxin-tested PBS at pH 7.4. For in vivo or cell-culture work, confirm the endotoxin level is below 0.1 EU/mL. If preparing PBS in-house, sterile-filter through a 0.22 µm membrane after preparation.

Step 3: Calculate Target Concentration

Use the molecular weight from the certificate of analysis, not a generic database value, since counterion salts affect actual mass.

Target Concentration Peptide Mass (1 mg) PBS Volume Required
1 mg/mL 1 mg 1.0 mL
0.5 mg/mL 1 mg 2.0 mL
0.1 mg/mL 1 mg 10.0 mL

Step 4: Add Solvent Gradually and Mix Gently

Add PBS in small increments to the lyophilized peptide. Avoid vortexing at high speed for extended periods, as mechanical shear can fragment sensitive sequences. Gentle swirling or brief low-speed vortexing for 5 to 10 seconds is sufficient for most hydrophilic peptides.

Step 5: Verify Dissolution and Filter

Inspect the solution visually for particulates. For critical applications, confirm concentration using UV absorbance at 280 nm if the peptide contains aromatic residues, or via HPLC for absolute quantification. Filter through a 0.22 µm syringe filter before aliquoting.

PBS vs. Alternative Solvents: Choosing the Right Buffer

Researchers working with a broad peptide library will encounter situations where PBS is not the optimal first choice. Understanding the alternatives is essential.

PBS vs. Alternative Solvents: Choosing the Right Buffer

Bacteriostatic water contains 0.9% benzyl alcohol, which inhibits microbial growth and extends the usable life of a reconstituted stock. It is commonly used for peptides intended for repeated withdrawal from the same vial. However, it lacks the buffering capacity of PBS and is not appropriate for pH-sensitive assays. Researchers exploring SS-31 peptide research and related mitochondria-targeted compounds often weigh bacteriostatic water against PBS depending on the assay format.

HEPES-buffered saline (HBS) offers a phosphate-free alternative at physiological pH, making it preferable for calcium-sensitive assays or any protocol where phosphate ions could interfere with signaling pathways. The tradeoff is higher cost and less universal availability.

Dilute acetic acid (0.1% to 1%) is the go-to primary solvent for hydrophobic or aggregation-prone peptides. After initial dissolution in acetic acid, the researcher then dilutes into PBS to reach physiological conditions, keeping the final acetic acid concentration below 0.01%.

DMSO is reserved for extremely hydrophobic sequences. Final DMSO concentration in cell-based assays should remain below 0.1% to avoid cytotoxicity.

For those sourcing peptides for structured research programs, working with a best peptide supplier that provides solubility guidance alongside the certificate of analysis removes much of the guesswork from solvent selection.

Storage and Handling of PBS-Reconstituted Peptide Stocks

Reconstitution is only half the protocol. Improper storage is one of the most common sources of data variability in peptide research.

Recommended storage practices for 2026:

  • Short-term use (less than 72 hours): Store at 2 to 8 degrees Celsius in a sealed, sterile vial. Minimize freeze-thaw cycles.
  • Medium-term storage (up to 4 weeks): Aliquot into single-use volumes and store at -20 degrees Celsius. Label each aliquot with peptide name, concentration, date, and lot number.
  • Long-term storage (beyond 4 weeks): Store at -80 degrees Celsius. Note that phosphate salts can precipitate during freezing; allow complete thaw and gentle mixing before use.
  • Light sensitivity: Many peptides degrade under UV exposure. Use amber vials or wrap clear vials in foil.

Researchers working with compounds such as SS-31 peptide or Mot-C peptide should follow the specific storage guidance provided with each product, as mitochondria-targeted and growth-hormone-related peptides can have unique stability profiles that modify general PBS storage rules.

For broader research contexts such as wound healing peptide studies or metabolic peptide investigations, maintaining a cold chain from reconstitution through assay setup is non-negotiable.

Conclusion

Phosphate Buffered Saline for Peptide Reconstitution: A Complete Research Protocol Guide comes down to three decisions: assess whether PBS suits the peptide's chemistry, execute the reconstitution with sterile technique and accurate concentration math, and store aliquots under conditions that prevent degradation. PBS earns its status as the most common reconstitution solvent because it is physiologically compatible, widely available, and well-characterized, but it is not appropriate for every peptide or every assay.

Actionable next steps for researchers:

  1. Always obtain and review the certificate of analysis before selecting a solvent.
  2. Default to PBS for hydrophilic, charge-bearing peptides destined for cell-based or in vivo work.
  3. Switch to bacteriostatic water, HBS, or acetic acid pre-dissolution when PBS chemistry creates stability or solubility concerns.
  4. Aliquot immediately after reconstitution and label every vial with full traceability information.
  5. Source peptides from a best peptide manufacturer that provides third-party purity testing, so the reconstitution protocol starts with a verified, high-quality substrate.

A disciplined approach to solvent selection and storage transforms peptide reconstitution from a potential failure point into a reliable, reproducible foundation for research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/phosphate-buffered-saline-for-peptide-reconstitution-a-complete-research-protoco.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:05:452026-09-14 13:05:45Phosphate Buffered Saline for Peptide Reconstitution: A Complete Research Protocol Guide
Where to Buy Glow Blend and Klow Blend Peptides Online: Research-Grade vs Cosmetic-Grade Sourcing and Quality Control

Where to Buy Glow Blend and Klow Blend Peptides Online: Research-Grade vs Cosmetic-Grade Sourcing and Quality Control

September 13, 2026/0 Comments/in Uncategorized/by

Less than 30% of peptide products sold online include a verifiable third-party Certificate of Analysis, yet buyers routinely pay premium prices assuming research-grade purity. For anyone navigating where to buy Glow Blend and Klow Blend peptides online, understanding the difference between research-grade and cosmetic-grade sourcing is not just a matter of preference; it directly affects the integrity of any study or protocol that depends on these compounds.

Key Takeaways

  • Glow Blend and Klow Blend are distinct multi-peptide formulations with different compositional targets and mechanisms of action.
  • Research-grade products must carry third-party Certificates of Analysis (COAs) confirming purity, sequence accuracy, and absence of contaminants.
  • Cosmetic-grade or cosmetic-positioned products may use the same ingredient names but lack the documentation required for rigorous research use.
  • Red flags in vendor marketing include vague purity claims, no HPLC data, and language implying direct human therapeutic use.
  • Sourcing from vendors who publish transparent COAs and maintain research-only disclaimers is the safest approach for legitimate research purposes.

Understanding Glow Blend and Klow Blend: Composition and Purpose

Understanding Glow Blend and Klow Blend: Composition and Purpose

Glow Blend is a multi-peptide formulation typically built around skin-targeted bioactive peptides such as GHK-Cu (copper tripeptide-1), Palmitoyl Tripeptide-1, and signal peptides like Leuphasyl. These components are selected for their studied roles in collagen synthesis signaling, oxidative stress modulation, and dermal matrix support. In a research context, Glow Blend is examined for its potential effects on fibroblast activity and extracellular matrix remodeling.

Klow Blend takes a different mechanistic angle. It is formulated around Klotho-derived peptide fragments, which are of significant interest in longevity and cellular senescence research. Klotho-related peptides are studied for their interactions with FOXO signaling pathways, fibroblast growth factor receptors, and potential senolytic-adjacent activity. Klow Blend is therefore positioned more firmly in the anti-aging and cellular biology research space, rather than the topical cosmetic space.

The distinction matters enormously when sourcing. Because Glow Blend overlaps with cosmetic ingredient categories, it occupies a gray zone where cosmetic-grade and research-grade products can appear nearly identical on a product page. Klow Blend, being less mainstream, is more consistently sold through research-oriented channels, but that does not guarantee quality by default.

For broader context on how peptide blends are structured and categorized, the Peptides 101 for Research-Use Only Buyers guide provides a strong foundation.

Research-Grade vs Cosmetic-Grade: What the Distinction Actually Means

Research-Grade vs Cosmetic-Grade: What the Distinction Actually Means

The terms "research-grade" and "cosmetic-grade" are not always defined consistently across the industry, which creates real confusion for buyers. Here is what each designation should mean in practice:

Research-Grade Standards

  • Purity of 98% or higher, confirmed by HPLC (High-Performance Liquid Chromatography)
  • Mass spectrometry verification of correct amino acid sequence
  • Endotoxin testing results included on the COA
  • Sterility or microbial testing documentation
  • Batch-specific COA linked to the product lot number
  • Clear "for research use only" labeling, not intended for human consumption

Cosmetic-Grade Standards

  • Purity thresholds are lower and often unspecified
  • COAs may be absent, generic, or not batch-specific
  • Formulated for topical application, not injection or reconstitution
  • May include preservatives, emulsifiers, or carrier ingredients not suitable for research
  • Often sold with marketing language implying direct skin or health benefits

"A COA without an HPLC chromatogram attached is not a COA, it is a label."

This distinction is especially critical for Glow Blend, where cosmetic serum brands and research peptide vendors may use nearly identical product names. A buyer who does not check for batch-specific HPLC data could easily purchase a cosmetic formulation while believing they have secured a research-grade compound.

Similar sourcing diligence applies to other research peptide blends. Buyers exploring BPC-157 and TB-500 blend products will recognize the same documentation requirements.

Where to Buy Glow Blend and Klow Blend Peptides Online: Vendor Evaluation Framework

Where to Buy Glow Blend and Klow Blend Peptides Online: Vendor Evaluation Framework

Knowing where to buy Glow Blend and Klow Blend peptides online requires a structured approach to vendor evaluation. The following framework helps separate credible research suppliers from cosmetic-adjacent or low-quality sources.

Step 1: Confirm Third-Party COA Availability

Every legitimate research-grade vendor publishes batch-specific COAs from independent laboratories. The COA should include:

  • HPLC purity percentage (target: 98%+)
  • Mass spectrometry confirmation
  • Endotoxin levels
  • The specific lot number matching the product being sold

If a vendor links to a generic or undated COA, treat it as a red flag.

Step 2: Evaluate Research-Only Disclaimers

Reputable vendors clearly state that their products are sold for laboratory and research purposes only, not for human use. Vendors who use language like "supports glowing skin" or "clinically shown to reduce wrinkles" without referencing controlled research are blurring the line between cosmetic marketing and research supply, and may not be held to research-grade standards.

Step 3: Assess Vendor Transparency

Look for vendors who publish:

  • Ingredient sourcing disclosures
  • Manufacturing location or GMP (Good Manufacturing Practice) compliance statements
  • Contact information for technical or scientific inquiries
  • Clear return and quality guarantee policies

Buyers sourcing other specialized peptides can apply the same framework. Resources like the guide on where to buy SS31 and Epithalon online demonstrate what transparent vendor communication looks like in practice.

Red Flags to Avoid

Common Red Flags in Peptide Vendor Marketing (2026)

  • Purity claims with no supporting HPLC data
  • COA dated more than 12 months ago with no batch reference
  • Product descriptions using therapeutic or cosmetic benefit language
  • No research-use-only disclaimer anywhere on the product page
  • Vague sourcing statements like “pharmaceutical grade” without documentation

Quality Control Practices: What Separates Top-Tier Suppliers

For both Glow Blend and Klow Blend, the highest-quality research suppliers in 2026 follow a consistent quality control model:

QC Element What to Look For
HPLC Testing Batch-specific chromatogram attached to COA
Mass Spec Sequence confirmation for each peptide component
Endotoxin Results below 1 EU/mg for injectable-grade research
Sterility Microbial testing documentation available
Packaging Lyophilized powder in sealed, labeled vials with lot number

Klow Blend, given its Klotho-derived peptide components, requires particular attention to sequence fidelity. Even minor synthesis errors in Klotho fragment peptides can alter receptor binding behavior, making mass spectrometry confirmation non-negotiable for serious research applications.

For researchers interested in how peptide endocrine interactions are documented and verified, the article on peptides and polypeptides in endocrine pharmacology offers useful mechanistic context.

Regulatory Context and the Telehealth Gray Zone

A growing number of telehealth and concierge wellness services in 2026 are incorporating peptide blends, including Glow Blend formulations, into supervised protocols. This creates a secondary market where research-grade compounds are sourced by practitioners for use in patient-adjacent contexts.

This practice exists in a regulatory gray zone. In the United States, peptides sold as research chemicals are not FDA-approved for human therapeutic use. Practitioners sourcing these compounds bear responsibility for verifying purity and safety documentation. Buyers in this space should be especially rigorous about COA verification and should not assume that a telehealth provider's use of a compound implies regulatory approval.

Understanding peptide dosing considerations is a related area where documentation quality directly affects research validity and safety.

Conclusion

Sourcing Glow Blend and Klow Blend peptides online in 2026 demands more than finding a vendor with a professional-looking website. The gap between cosmetic-grade and research-grade products is real, measurable, and consequential for anyone conducting legitimate research or operating within a supervised protocol.

Actionable next steps:

  1. Request batch-specific COAs with HPLC chromatograms before purchasing any Glow or Klow Blend product.
  2. Verify that the vendor uses clear research-only disclaimers and avoids therapeutic benefit language.
  3. Cross-reference endotoxin and mass spectrometry data for Klow Blend products specifically, given the sequence sensitivity of Klotho-derived fragments.
  4. Avoid vendors who cannot provide direct contact for scientific or technical questions.
  5. Use the vendor evaluation framework above as a repeatable checklist for every new supplier.

Quality documentation is not a bureaucratic formality, it is the foundation of reproducible, trustworthy research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/where-to-buy-glow-blend-and-klow-blend-peptides-online-research-grade-vs-cosmeti.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-13 13:04:202026-09-13 13:04:20Where to Buy Glow Blend and Klow Blend Peptides Online: Research-Grade vs Cosmetic-Grade Sourcing and Quality Control
Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models

Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models

September 13, 2026/0 Comments/in Uncategorized/by

Nearly 64 million people worldwide live with heart failure, and a large proportion of them carry simultaneous kidney dysfunction, a dual burden that no single drug has fully solved. The intersection of spironolactone, cardiorenal pathways, and tissue-repair peptides: how BPC-157 and TB-500 complement classic heart and kidney drug models is now a serious focus in advanced cardiometabolic research. Understanding where established mineralocorticoid receptor antagonists (MRAs) succeed, where they fall short, and how regenerative peptides might fill mechanistic gaps is increasingly relevant for researchers and clinicians alike.

Key Takeaways

  • Spironolactone blocks aldosterone receptors to reduce fibrosis and fluid retention, but large trials in specific populations, including dialysis patients, show limits to its cardiovascular benefit.
  • Newer non-steroidal MRAs like finerenone demonstrate stronger cardiorenal outcome data, signaling that the MRA class is still evolving.
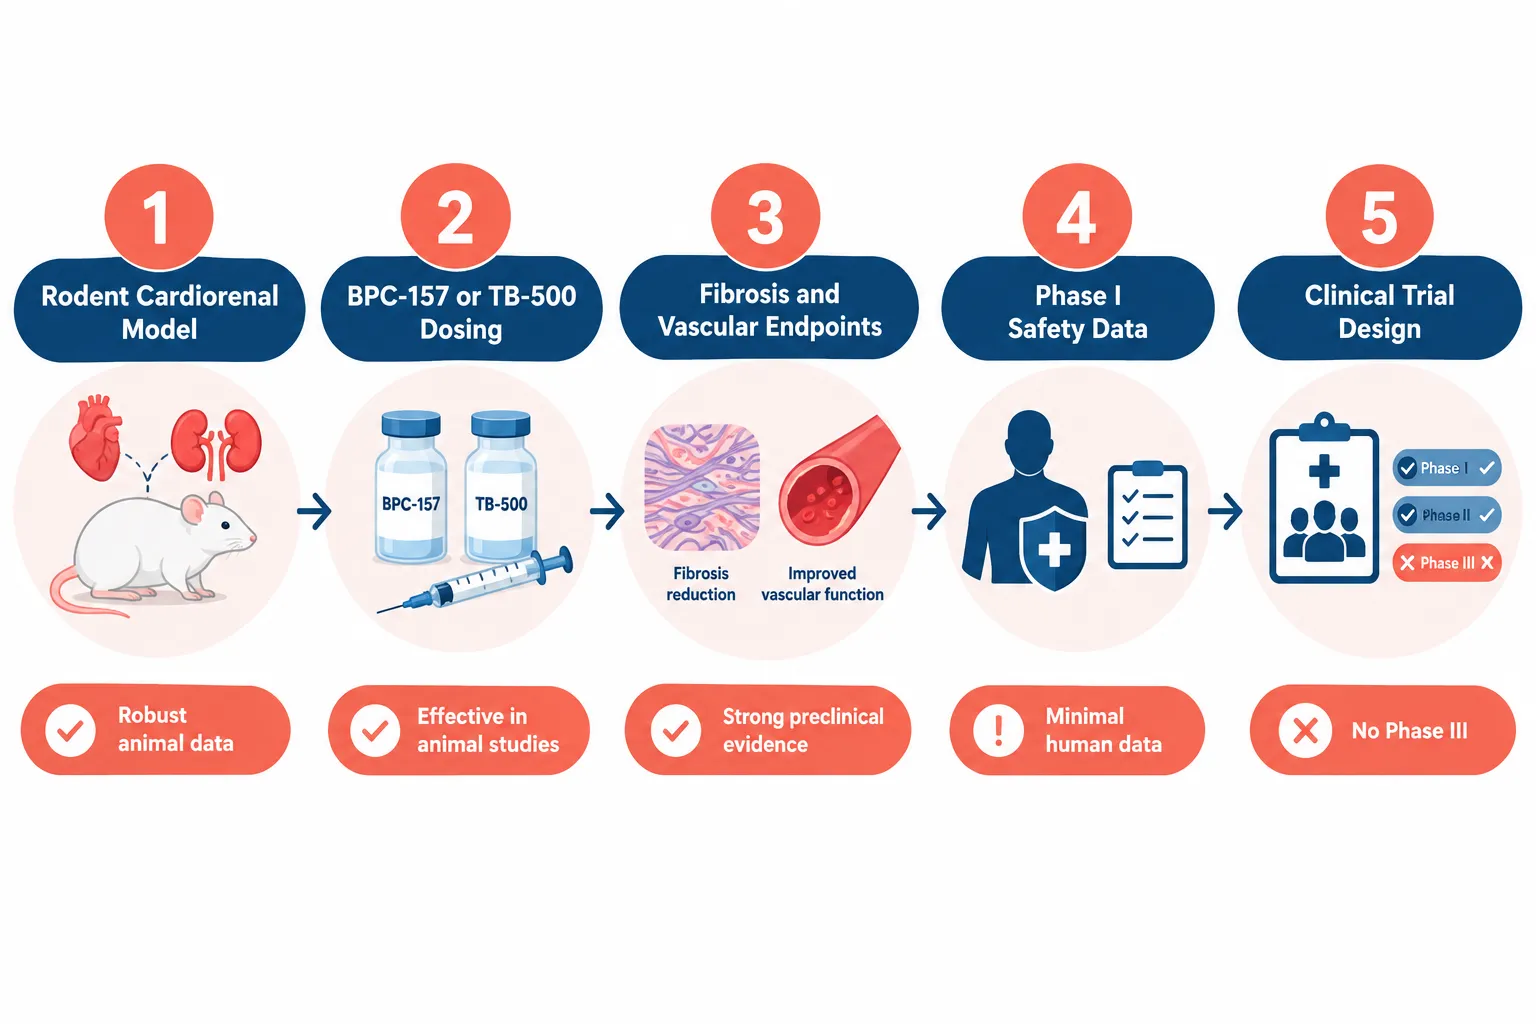
  • BPC-157 and TB-500 operate through vascular and tissue-repair pathways that are mechanistically distinct from neurohormonal blockade.
  • Both peptides have compelling animal-model data for cardiac and vascular endpoints, but human clinical evidence remains early and limited.
  • Combining neurohormonal drugs with tissue-repair peptides is a conceptual frontier, not yet a validated clinical strategy.

How Spironolactone Shapes Cardiorenal Pathways

How Spironolactone Shapes Cardiorenal Pathways

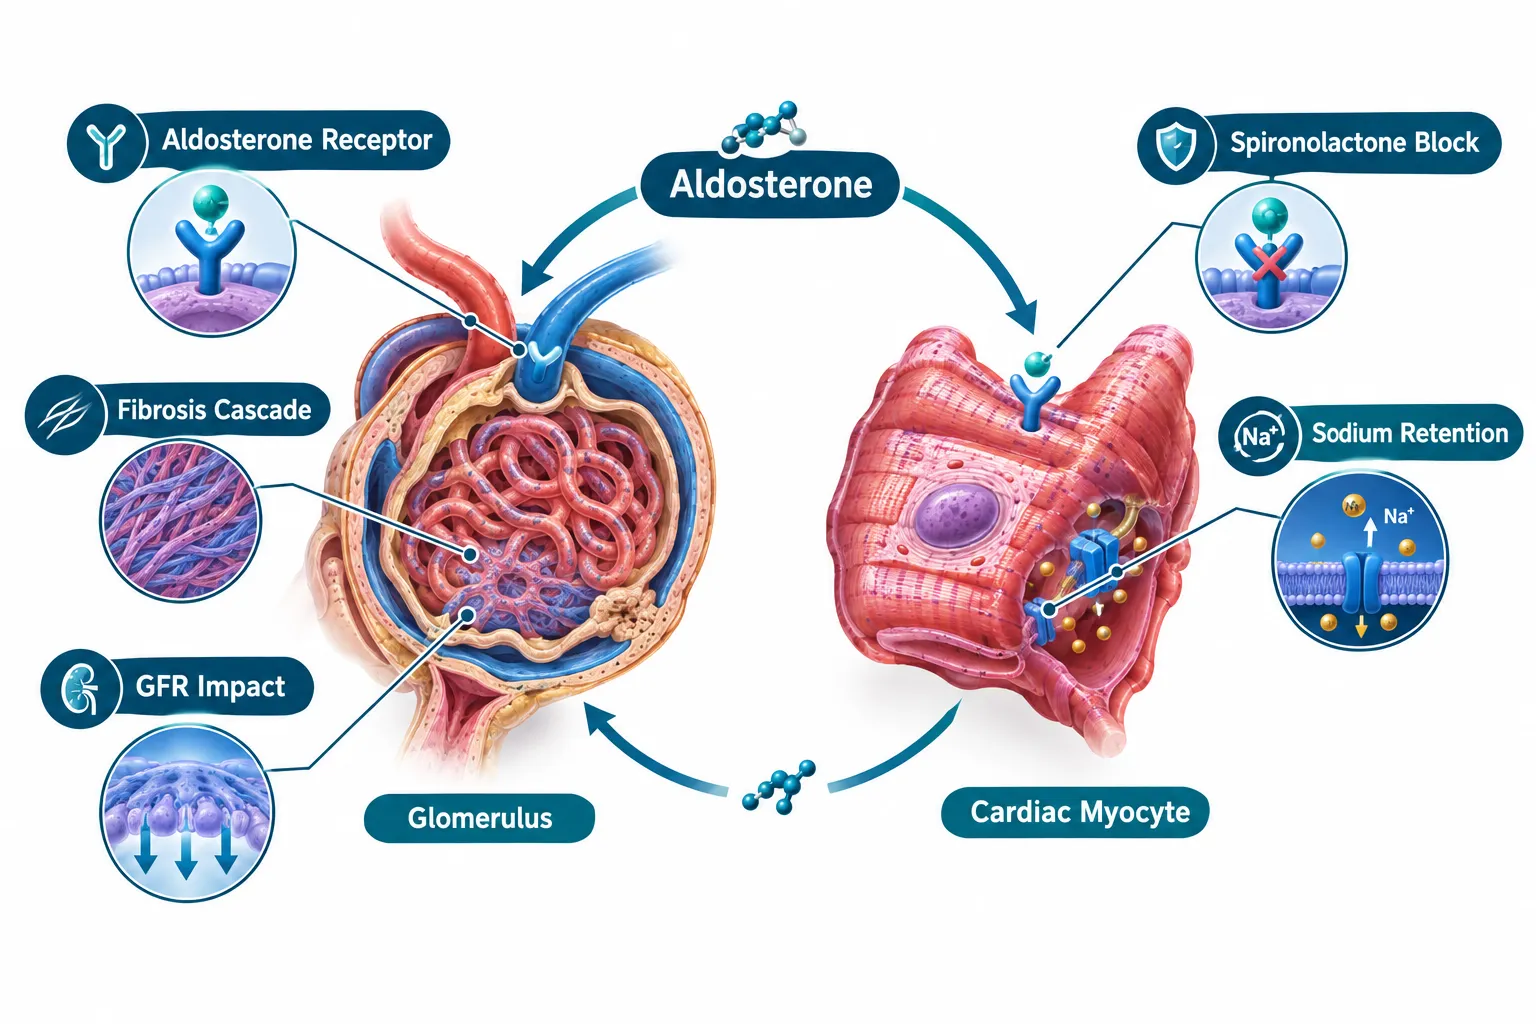
Spironolactone has been a cornerstone of heart failure therapy for decades. It works by blocking aldosterone receptors in the kidney, heart, and vasculature, reducing sodium retention, lowering blood pressure, and most importantly, suppressing the fibrotic signaling that aldosterone drives in cardiac and renal tissue.

The fibrosis connection is critical. Aldosterone excess promotes collagen deposition in the myocardium and glomeruli. By blocking this pathway, spironolactone reduces myocardial stiffness and slows the structural decline that characterizes both heart failure with preserved ejection fraction (HFpEF) and chronic kidney disease (CKD).

However, clinical trial results have complicated the picture:

  • The SPIRIT-HF program, running from 2018 through 2024, produced neutral outcomes for spironolactone in HFpEF and heart failure with mildly reduced ejection fraction (HFmrEF).
  • A large trial in dialysis patients was stopped early for futility, spironolactone showed no cardiovascular benefit in that population.
  • The CLEAR SYNERGY post-MI trial found that spironolactone reduced new or worsening heart failure, but did not significantly reduce major cardiovascular events overall.

These results do not dismiss spironolactone, they clarify its boundaries. The pragmatic SPIRRIT-HFpEF registry continues to test MRAs in real-world HFpEF populations, acknowledging that patient selection matters enormously.

Finerenone, a third-generation non-steroidal MRA, has now produced robust cardiorenal outcome data across both heart failure and diabetic kidney disease populations. Its greater receptor selectivity reduces the side-effect burden of older steroidal MRAs while maintaining anti-fibrotic potency. The modern cardiorenal therapeutic core now integrates MRAs alongside SGLT2 inhibitors and incretin-based therapies, a multi-pathway approach that reflects how complex cardiorenal disease truly is.

"The cardiorenal axis is not a single switch, it is a network of overlapping signals, and blocking one node rarely resolves the whole system."

BPC-157 and TB-500: Tissue-Repair Mechanisms in Cardiorenal Research

BPC-157 and TB-500: Tissue-Repair Mechanisms in Cardiorenal Research

This is where the conversation about spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, becomes genuinely novel. These two peptides work through entirely different biological levers than MRAs.

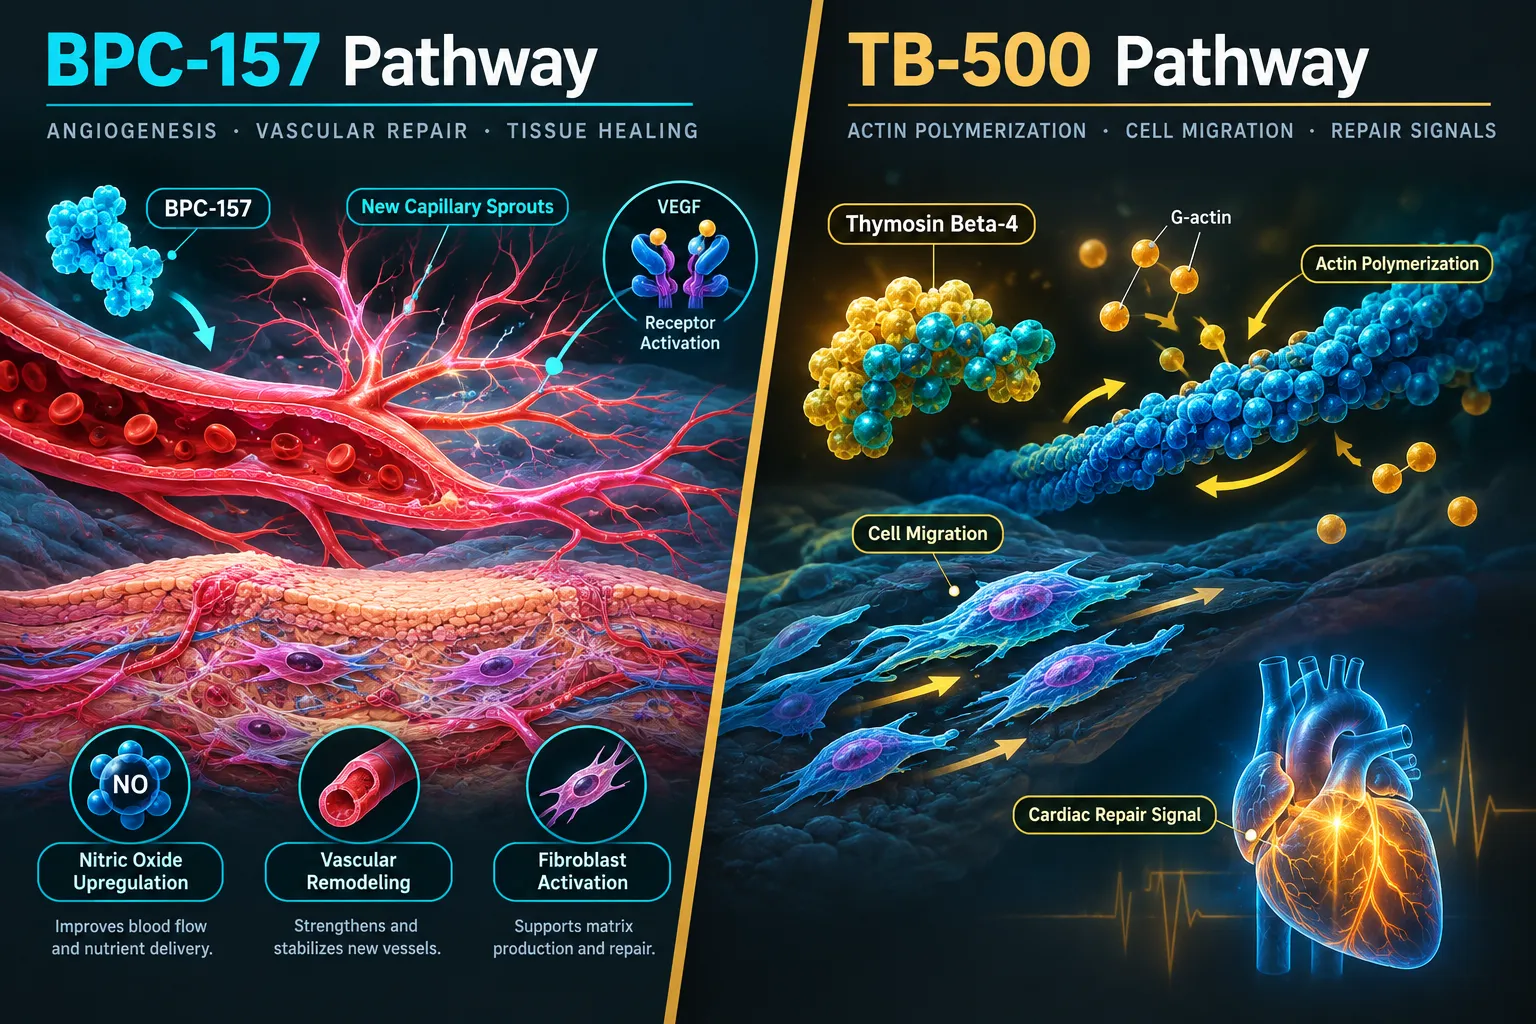
BPC-157 (Body Protection Compound-157) is a synthetic pentadecapeptide derived from a gastric protein. In animal models, it has demonstrated:

  • Upregulation of nitric oxide synthase, improving vascular tone
  • Promotion of angiogenesis through VEGF receptor pathways
  • Reduction of fibrotic markers in cardiac and renal tissue
  • Accelerated healing in wound models relevant to ischemic injury

TB-500 (synthetic thymosin beta-4) targets actin polymerization and cell migration. In small animal cardiac studies, it has shown potential to:

  • Stimulate cardiac progenitor cell activation after ischemic injury
  • Reduce scar formation in post-MI myocardium
  • Support endothelial repair and vascular remodeling

These are properties that MRAs simply do not possess. Spironolactone blocks a hormonal signal; BPC-157 and TB-500 actively promote structural repair. Researchers exploring wound healing peptides in vascular contexts recognize this distinction as foundational.

The critical caveat: almost all of this evidence comes from rodent and small-animal models. Current human trials for BPC-157 focus on musculoskeletal repair, not cardiorenal indications. TB-500 has small human studies with mixed signals and no Phase III data. Neither peptide is approved by any regulatory agency; BPC-157 is classified as a Category 2 bulk substance in several jurisdictions.

For researchers sourcing compounds for preclinical work, working with a best peptide manufacturer that provides verified purity documentation is essential for valid experimental outcomes.

Mechanistic Complementarity: Where the Two Models Meet

Mechanistic Complementarity: Where the Two Models Meet

The most intellectually productive framing of spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, is mechanistic layering, not replacement.

Mechanism Spironolactone / Finerenone BPC-157 TB-500
Aldosterone blockade Yes No No
Anti-fibrotic signaling Yes (indirect) Yes (direct, animal data) Partial (animal data)
Angiogenesis promotion No Yes (animal data) Yes (animal data)
Cardiac structural repair No Emerging Emerging
Human outcome data Robust Minimal Minimal

The table above illustrates why these are complementary, not competing, research targets. MRAs address the neurohormonal driver of cardiorenal damage. Tissue-repair peptides, if their animal-model promise translates to humans, could address the downstream structural consequences, the scarring, the vascular rarefaction, the impaired healing that persists even after hormonal blockade.

Researchers working with 5 amino peptide compounds and related short-chain structures are increasingly interested in how these molecules interact with established pharmacological frameworks. Similarly, interest in GHK-Cu peptide for vascular and tissue remodeling endpoints reflects a broader shift toward regenerative mechanisms in cardiometabolic research.

The integrated cardiorenal model, combining MRAs, SGLT2 inhibitors, and incretin therapies, already demonstrates that multi-pathway intervention outperforms single-target strategies. The logical next research question is whether tissue-repair peptides can add a structural-regeneration layer on top of that neurohormonal foundation.

Sourcing quality compounds from a verified best peptide supplier remains a prerequisite for any preclinical work attempting to answer that question rigorously.

Conclusion

The relationship between spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, represents one of the more promising conceptual frontiers in cardiometabolic research in 2026. Spironolactone and its successor finerenone have defined the neurohormonal anti-fibrotic standard, even as large trials have refined the populations most likely to benefit. BPC-157 and TB-500 offer a mechanistically distinct toolkit, vascular repair, angiogenesis, and structural healing, that animal models suggest could layer meaningfully onto established pharmacology.

Actionable next steps for researchers:

  1. Review the current SPIRRIT-HFpEF registry data to understand real-world MRA performance benchmarks.
  2. Design preclinical cardiorenal studies that include both fibrosis endpoints (relevant to MRAs) and vascular repair endpoints (relevant to BPC-157 and TB-500).
  3. Demand purity-verified peptide compounds for any experimental work to ensure data validity.
  4. Monitor emerging Phase I human data on BPC-157 musculoskeletal trials, the safety signals from those studies will inform whether cardiorenal indications are feasible.
  5. Consider finerenone's non-steroidal MRA profile as the appropriate comparator benchmark when designing combination studies.

The gap between animal-model promise and clinical validation remains wide. Closing it requires rigorous, well-sourced research, and a clear understanding of what each drug class can and cannot do.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/spironolactone-cardiorenal-pathways-and-tissue-repair-peptides-how-bpc-157-and-t.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-13 13:04:082026-09-13 13:04:08Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models
Lorazepam, Buspirone, and Nasal Spray Peptides: How Semax, Selank, and Klow Nasal Formulations Differ From Classic Anxiolytics in Lab Studies

Lorazepam, Buspirone, and Nasal Spray Peptides: How Semax, Selank, and Klow Nasal Formulations Differ From Classic Anxiolytics in Lab Studies

September 13, 2026/0 Comments/in Uncategorized/by

Anxiety disorders affect roughly one in three adults at some point in their lives, yet the two most prescribed drug classes for anxiety, benzodiazepines and azapirones, carry well-documented trade-offs that researchers have spent decades trying to solve. The comparison of lorazepam, buspirone, and nasal spray peptides, specifically how Semax, Selank, and Klow nasal formulations differ from classic anxiolytics in lab studies, has become one of the more active areas of preclinical pharmacology in 2026. Understanding the mechanistic differences between these compound classes is essential for anyone following peptide research, neuropharmacology, or CNS drug development.

Key Takeaways

  • Lorazepam works through GABA-A receptor modulation, producing fast but sedating and dependence-prone anxiolysis.
  • Buspirone partially agonizes the 5-HT1A receptor, avoiding sedation but requiring weeks for full effect.
  • Semax and Selank are intranasal peptides with distinct receptor targets, cognitive endpoints, and minimal sedation in animal models.
  • Klow nasal blends combine multiple peptides but currently lack formal anxiolytic trial data.
  • Intranasal delivery bypasses hepatic first-pass metabolism, giving peptides a bioavailability advantage that oral routes cannot match.

Receptor Targets: Where Classic Drugs and Peptides Diverge

Receptor Targets: Where Classic Drugs and Peptides Diverge

The most fundamental difference between classic anxiolytics and peptide nasal sprays lies in their receptor targets.

Lorazepam is a benzodiazepine. It binds to the GABA-A receptor complex and enhances chloride ion influx, effectively slowing neuronal firing across the central nervous system. The result is fast, reliable anxiolysis, but it comes packaged with sedation, psychomotor impairment, and a significant dependence liability with repeated use. Tolerance builds within weeks, and abrupt discontinuation can trigger rebound anxiety or seizures.

Buspirone operates through a completely different pathway. As a partial agonist at the 5-HT1A serotonin receptor, it modulates serotonergic tone without touching GABA channels. This sidesteps sedation and dependence risk, but the trade-off is a slow onset, clinical effect typically requires two to four weeks of consistent dosing. Buspirone also has a narrower symptom profile, performing better on generalized anxiety than on panic or phobic subtypes.

Semax and Selank diverge from both of these mechanisms in ways that make direct comparison difficult. Semax research shows that this heptapeptide analog of ACTH(4-7) primarily stimulates brain-derived neurotrophic factor (BDNF) production and modulates dopaminergic and serotonergic signaling. Its anxiolytic-adjacent effects in rodent models appear secondary to broader neuroprotective and cognitive-enhancing actions, not direct receptor sedation.

Selank, a synthetic analog of the endogenous peptide tuftsin, shows a more direct anxiolytic profile in animal studies. It appears to influence GABAergic activity and serotonin metabolism simultaneously, producing anxiety reduction without the sedation or withdrawal effects seen with benzodiazepines. Comparative studies on Selank vs Semax suggest that while both reduce stress markers in rodents, Selank's anxiolytic signal is more consistent and Semax's cognitive benefits are more pronounced.

Intranasal Delivery and Bioavailability: Why the Route Matters

Intranasal Delivery and Bioavailability: Why the Route Matters

The delivery route is not a minor detail, it is central to understanding why peptide nasal sprays are studied at all.

Oral administration of peptides faces a brutal pharmacokinetic obstacle: proteolytic enzymes in the gut degrade most peptide bonds before absorption, and any fraction that does absorb encounters hepatic first-pass metabolism before reaching systemic circulation. The result is negligible bioavailability for most unmodified peptides taken by mouth.

Intranasal delivery bypasses both barriers. The olfactory epithelium and the cribriform plate offer a direct anatomical pathway to the CNS, allowing peptides to enter brain tissue without crossing the blood-brain barrier through conventional routes. Studies on Semax nasal spray formulations show measurable CNS activity at doses far lower than would be required orally, and onset is substantially faster than buspirone's multi-week timeline.

Key distinction: Classic anxiolytics are optimized for oral bioavailability. Peptide nasal sprays exploit a different anatomical route entirely, one that classic drug formulation never needed to consider.

Lorazepam, by contrast, achieves near-complete oral absorption through conventional gastrointestinal uptake and does not require intranasal delivery. Buspirone has moderate oral bioavailability but is also subject to significant first-pass metabolism, which is why its clinical doses are relatively high.

For researchers reviewing Semax research protocols, intranasal dosing typically ranges from 200 to 600 micrograms per day in animal models, with human exploratory use reported in Russian clinical literature at similar microgram-range doses. Selank intranasal studies use comparable ranges. These doses are orders of magnitude smaller than typical benzodiazepine or buspirone doses, reflecting the efficiency of the nasal-to-CNS route.

Cognitive Endpoints, Side-Effect Profiles, and the Klow Question

Cognitive Endpoints, Side-Effect Profiles, and the Klow Question

The side-effect comparison between these compound classes is where the practical research interest concentrates.

Feature Lorazepam Buspirone Semax / Selank Klow Blends
Primary target GABA-A 5-HT1A BDNF / GABAergic Multi-peptide
Sedation High None None observed Unknown
Dependence risk High Low Not reported Unknown
Cognitive effects Blunting Neutral Enhancement Uncharacterized
Onset Minutes 2-4 weeks Hours (intranasal) Not established
Human trial data Extensive Extensive Limited None

Lorazepam consistently blunts working memory and reaction time in controlled studies, effects that persist beyond the anxiolytic window. Buspirone avoids this but offers no cognitive benefit. Semax, in multiple rodent and limited human studies, shows the opposite pattern: improved memory consolidation, faster learning acquisition, and enhanced neuroplasticity markers alongside stress reduction.

Selank's cognitive profile is more neutral than Semax's but still avoids the blunting seen with benzodiazepines. In studies comparing anxiolytic efficacy, Selank reduced anxiety-like behavior in elevated plus-maze and open-field tests without impairing locomotor performance, a finding that stands in direct contrast to lorazepam's profile.

Klow nasal formulations represent a newer category of multi-peptide blends. These products combine several peptide compounds in a single intranasal delivery system, targeting multiple pathways simultaneously. However, as of 2026, no formal anxiolytic trials exist for Klow-style blends. The mechanistic rationale is plausible given the individual peptide data, but the absence of controlled trial data means efficacy and safety claims remain speculative. Researchers interested in the broader landscape of wholesale peptides for sale in research contexts should treat Klow formulations as hypothesis-generating rather than evidence-supported.

The authority of current evidence also deserves honest assessment. Semax and Selank have the strongest data sets among the peptide group, but most studies originate from Russian research institutions and involve relatively small sample sizes. Replication in Western clinical settings remains limited. This does not invalidate the findings, but it does mean that direct head-to-head comparisons with lorazepam or buspirone at the clinical trial level do not yet exist.

For those exploring the broader peptide research space, resources on peptides and polypeptides in endocrine pharmacology provide useful context on how peptide compounds interact with receptor biology across different systems.

Conclusion

The mechanistic gap between lorazepam, buspirone, and intranasal peptides like Semax, Selank, and Klow is not simply a matter of degree, it reflects fundamentally different pharmacological philosophies. Classic anxiolytics target established receptor systems with decades of clinical data but carry sedation, dependence, and cognitive cost. Peptide nasal sprays exploit the nasal-to-CNS route to deliver compounds that appear to modulate anxiety through neuroprotective and neurotrophic pathways, with a side-effect profile that animal models suggest is substantially cleaner.

Actionable next steps for researchers and informed readers:

  • Review the primary Semax and Selank literature from Russian clinical sources alongside any available Western replication studies before drawing efficacy conclusions.
  • Treat Klow multi-peptide blends as research-stage compounds requiring formal trial data before anxiolytic claims can be substantiated.
  • Recognize that intranasal bioavailability data does not automatically translate to clinical equivalence with orally dosed classic anxiolytics.
  • Follow emerging Semax nasal spray research for updates on human dosing and cognitive endpoint data as the field matures in 2026.

The comparison of lorazepam, buspirone, and nasal spray peptides, and how Semax, Selank, and Klow nasal formulations differ from classic anxiolytics in lab studies, will only sharpen as controlled human trials close the evidence gap between preclinical promise and clinical proof.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/lorazepam-buspirone-and-nasal-spray-peptides-how-semax-selank-and-klow-nasal-for.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-13 13:04:052026-09-13 13:04:05Lorazepam, Buspirone, and Nasal Spray Peptides: How Semax, Selank, and Klow Nasal Formulations Differ From Classic Anxiolytics in Lab Studies
Complement-Dependent Cytotoxicity, Immune Assays, and Safety Considerations in GLP-3, BPC-157, and Novel Peptide Studies

Complement-Dependent Cytotoxicity, Immune Assays, and Safety Considerations in GLP-3, BPC-157, and Novel Peptide Studies

September 13, 2026/0 Comments/in Uncategorized/by

Fewer than one in ten novel peptides entering preclinical development in 2026 has a published, peer-reviewed complement-dependent cytotoxicity (CDC) dataset attached to its safety profile. That gap matters enormously, because complement activation is one of the fastest routes by which an injected or infused peptide can trigger unintended immune cell lysis, inflammation, or vascular disruption. Understanding complement-dependent cytotoxicity, immune assays, and safety considerations in GLP-3, BPC-157, and novel peptide studies is no longer optional for responsible research, it is the foundation of a credible preclinical safety package.

Key Takeaways

  • Complement-dependent cytotoxicity (CDC) is an IgG/IgM-driven effector mechanism that can cause target cell lysis when complement proteins are activated in the presence of a peptide or antibody.
  • Four main assay formats, dye influx, dye release, metabolic, and ATP-luminescence, each measure CDC differently, and choosing the wrong one can produce misleading safety data.
  • Published CDC datasets for BPC-157, GHK-Cu, and MOTS-c are largely absent from the scientific literature as of mid-2026, creating a critical regulatory and safety gap.
  • The U.S. FDA classifies BPC-157 as a Category 2 bulk drug substance and states that insufficient clinical safety information exists to characterize its full safety profile.
  • Researchers and manufacturers should integrate CDC screening into early-stage preclinical batteries, not as a late add-on, and document peptide aggregation state before each assay run.

What Is Complement-Dependent Cytotoxicity and Why It Matters for Peptide Research

What Is Complement-Dependent Cytotoxicity and Why It Matters for Peptide Research

Complement-dependent cytotoxicity is an effector mechanism of the immune system. When IgG or IgM antibodies bind to a target cell surface, they recruit the C1q protein, triggering a cascade through the classical complement pathway. The end product is the membrane attack complex (MAC), a pore-forming structure that punches through the lipid bilayer and causes osmotic cell lysis.

In the context of peptide research, CDC becomes relevant whenever a synthetic peptide, or the antibodies it induces, interacts with cell surfaces in a way that activates complement. This is not a theoretical concern. Peptides that modulate immune or vascular pathways, including tissue-repair and receptor-targeted candidates, are structurally capable of engaging complement proteins, particularly if they aggregate or form oligomeric structures in solution.

Why aggregation state matters: Aggregated peptide fractions activate complement at significantly lower concentrations than monomeric forms. Before any CDC assay, researchers should characterize the peptide's aggregation state using dynamic light scattering. Skipping this step is one of the most common protocol errors identified in peptide laboratories in 2026.

"Absence of severe toxicity in animal models does not rule out immunogenicity or complement activation risks in humans."

For researchers working with GLP-3 peptide candidates or tissue-repair compounds, this mechanistic background is the starting point for designing a defensible immune safety evaluation.

Complement-Dependent Cytotoxicity, Immune Assays, and Safety Considerations: Assay Formats Compared

Complement-Dependent Cytotoxicity, Immune Assays, and Safety Considerations: Assay Formats Compared

Not all CDC assays are equal. A 2026 systematic review of major assay formats demonstrated that the choice of readout method can significantly alter how complement-mediated killing is quantified. The four main categories are:

Assay Format Readout Mechanism Key Strength Key Limitation
Dye Influx Propidium iodide enters lysed cells High sensitivity Background in damaged cells
Dye Release Calcein-AM leaks from cytoplasm Low background noise Requires pre-loading step
Metabolic MTT, XTT, or Alamar Blue activity Broad dynamic range Indirect cell death measure
ATP Luminescence CellTiter-Glo viability signal Quantitative, fast Reagent cost, lysis artifacts

A standardized CDC assay configuration recommended for peptide labs includes:

  1. Target cells expressing the relevant antigen or receptor
  2. Peptide-specific IgG/IgM or the test peptide itself
  3. Fresh rabbit or human serum as complement source (never heat-inactivated for the test condition)
  4. Serum at 10-25% v/v concentration
  5. Incubation at 37 degrees Celsius for 60-120 minutes
  6. Readout via LDH release, propidium iodide uptake, trypan blue exclusion, or luminescence

The essential negative control is heat-inactivated serum. Omitting this control, which destroys complement activity while preserving antibody function, is a frequent and consequential error. The standard cytotoxicity formula used in luminescence-based CDC is: % cytotoxicity = 100 x (1 – E/S), where E is luminescence with the experimental antibody and S is luminescence with serum alone.

For receptor-targeted peptides, the assay cell line must express the relevant receptor. Using a cell line that lacks the target receptor will produce false-negative CDC results, a critical consideration for GLP-3 R peptide constructs and other receptor-specific candidates.

Researchers should also probe both classical and alternative complement pathways using pathway-specific inhibitors: C1q depletion for the classical pathway and Factor D inhibition for the alternative pathway. This mechanistic layering distinguishes true CDC from non-specific cytotoxicity.

Safety Considerations in GLP-3, BPC-157, and Novel Peptide Studies: Regulatory and Data Gaps

Safety Considerations in GLP-3, BPC-157, and Novel Peptide Studies: Regulatory and Data Gaps

The most pressing safety issue in 2026 is not what the existing CDC data shows, it is what data does not yet exist. Formal, peer-reviewed CDC assay datasets for BPC-157, GHK-Cu, and MOTS-c are largely absent from the published scientific record. This gap directly complicates risk assessment for cosmetic, research, and healing peptide formulations.

BPC-157 regulatory status is particularly instructive. The U.S. FDA Pharmacy Compounding Advisory Committee classifies BPC-157 as a Category 2 bulk drug substance and explicitly states that insufficient clinical safety information exists to characterize the safety profile of BPC-157 free base and BPC-157 acetate. While animal studies in rats and beagle dogs at doses up to 20 mg/kg found no lethal outcomes or organ toxicity on histopathological examination, preclinical safety margins in animals do not translate directly to human immunogenicity risk.

Clinical guidance for healing peptides, including BPC-157 and TB-500, characterizes BPC-157 as having lower theoretical immune risk relative to some other agents but still recommends monitoring for local and systemic infection signs at injection sites. TB-500 use is advised against in transplant recipients due to immune modulation concerns, a reminder that even well-tolerated peptides can pose clinically significant immunologic risks in special populations.

For multi-peptide blends, industry guidance recommends:

  • Running individual component wells alongside the full blend
  • Tracking purity with certificates of analysis for every lot
  • For copper-containing peptides like GHK-Cu, distinguishing copper-specific cytotoxicity from complement-mediated effects with appropriate controls
  • Including excipient-only controls to determine whether formulation vehicles contribute to complement activation

Researchers exploring peptides 101 fundamentals will find that understanding CDC is inseparable from understanding how novel peptide structures interact with innate immune defense systems.

Control structure for a rigorous CDC experiment:

  • Positive control: known complement-activating antibody
  • Negative control: peptide-free vehicle
  • Peptide-alone control: no complement added (isolates direct cytotoxicity)
  • Complement-alone control: detects non-specific lysis

Industry guidance for 2026 is unambiguous: CDC screening should run in parallel with standard cytotoxicity panels from the earliest stages of preclinical development, not as a late-stage add-on. This applies equally to lab-tested peptides entering any formal research protocol and to novel candidates like GLP-3 RT 20mg nasal spray formulations where mucosal complement exposure adds another layer of complexity.

Looking ahead, regulatory authorities and institutional review boards are expected to require standardized CDC and complement-activation panels as part of GLP-grade immunotoxicology packages for any new peptide entering human studies. Industry practice is shifting toward routine complement pathway profiling, aggregation characterization, and harmonized assay formats, particularly aligning luminescence versus dye-influx readouts, so that safety data becomes comparable across laboratories.

Conclusion

Complement-dependent cytotoxicity, immune assays, and safety considerations in GLP-3, BPC-157, and novel peptide studies represent one of the most underdeveloped areas of preclinical peptide science in 2026. The immunology is well understood; the application to specific peptide candidates is not.

Actionable next steps for researchers and manufacturers:

  1. Characterize aggregation state using dynamic light scattering before every CDC assay run, monomeric, oligomeric, and aggregated fractions should be tested separately.
  2. Select the assay format deliberately, luminescence-based ATP readouts offer quantitative precision, while propidium iodide influx provides high sensitivity for membrane damage detection.
  3. Always include heat-inactivated serum as a negative control and complement-alone wells to detect non-specific lysis.
  4. Probe both complement pathways using C1q depletion and Factor D inhibition to distinguish classical from alternative activation.
  5. Close the data gap, any organization working with BPC-157, GHK-Cu, GLP-3 candidates, or tissue-repair peptides should prioritize generating and publishing CDC safety data as part of a complete preclinical immunotoxicology package.

The field is moving toward mandatory complement profiling. Researchers who build these endpoints into their protocols now will be better positioned for regulatory review and will contribute to a safer, more credible peptide research ecosystem.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/complement-dependent-cytotoxicity-immune-assays-and-safety-considerations-in-glp.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-13 13:04:032026-09-13 13:04:03Complement-Dependent Cytotoxicity, Immune Assays, and Safety Considerations in GLP-3, BPC-157, and Novel Peptide Studies
Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design

Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design

September 13, 2026/0 Comments/in Uncategorized/by

Participants in the TRIUMPH-1 Phase 3 trial lost an average of 28 to 30 percent of their body weight over 80 to 104 weeks, a figure that would have seemed implausible in obesity pharmacology just five years ago. That single data point from retatrutide's pivotal program captures why Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design has become one of the most closely watched conversations in metabolic medicine. The compound, informally called "GLP-3" because it adds glucagon receptor agonism on top of the GLP-1 and GIP dual-agonism already seen in tirzepatide, is forcing researchers to rethink how trials are designed, how endpoints are selected, and how combination strategies should be structured.

Key Takeaways

  • Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, earning the informal label "GLP-3" in research circles.
  • Phase 3 TRIUMPH trials are reporting weight loss figures of 28 to 30 percent, well above prior incretin benchmarks.
  • TRANSCEND-T2D-1 data show roughly 17 percent weight loss alongside strong glycemic control at 40 weeks.
  • Triple agonist results are pushing trial designers toward longer durations, multi-system endpoints, and broader inclusion criteria.
  • A broader pipeline, including Novo Nordisk's UBT251 and early quintuple agonist candidates, is accelerating the shift from single-target to multi-target metabolic drug development.

What "GLP-3" Actually Means: The Triple Receptor Mechanism

The nickname "GLP-3" is not an official receptor designation but a shorthand that reflects retatrutide's three-pronged mechanism. By co-activating the glucagon-like peptide-1 receptor, the glucose-dependent insulinotropic polypeptide receptor, and the glucagon receptor, the molecule targets energy intake, insulin sensitivity, and hepatic glucose output simultaneously.

What "GLP-3" Actually Means: The Triple Receptor Mechanism

This layered approach distinguishes retatrutide from earlier incretin therapies. GLP-1 agonism suppresses appetite and slows gastric emptying. GIP agonism enhances insulin secretion and may improve fat metabolism. Glucagon receptor agonism drives energy expenditure and accelerates hepatic fat clearance, a feature with direct implications for metabolic-associated steatotic liver disease (MASLD) research.

For researchers exploring the broader landscape of polypeptide peptides in cardiometabolic models, the triple agonist profile represents a meaningful departure from classic small-molecule drugs. Those interested in sourcing reference compounds for preclinical work can review options such as the GLP-3R 30mg Peptide GA8 or the GLP-3 Reta 30mg to understand the structural variants in active use.

Key receptor targets at a glance:

Receptor Primary Metabolic Effect
GLP-1R Appetite suppression, insulin secretion
GIPR Enhanced insulin response, fat metabolism
Glucagon R Energy expenditure, hepatic fat clearance

How Triple Agonist Trial Data Is Changing Metabolic Study Design

The TRIUMPH program illustrates how Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design is influencing the entire field, not just the Eli Lilly pipeline. TRIUMPH-1 enrolled adults with obesity but without type 2 diabetes and ran to 80 to 104 weeks, significantly longer than most prior Phase 3 obesity trials. TRIUMPH-2 and TRIUMPH-3 extend the complexity further by enrolling participants with obesity plus serious complications, including type 2 diabetes and established cardiovascular disease.

How Triple Agonist Trial Data Is Changing Metabolic Study Design

The TRANSCEND-T2D-1 diabetes-focused trial adds another layer. At 40 weeks, participants showed approximately 17 percent weight loss alongside robust glycemic control, outcomes that are prompting endocrinology researchers to reconsider whether weight loss should be a primary rather than secondary endpoint in diabetes trials.

"The shift is not just about better drugs, it is about better questions. Triple agonist data demands that trials ask what happens to the liver, the heart, and the vasculature simultaneously."

Several design changes are now appearing across the metabolic research landscape:

  • Longer trial durations, 80 to 104 weeks is becoming a new baseline for obesity studies.
  • Broader inclusion criteria, cardiovascular and hepatic comorbidities are now inclusion factors rather than exclusion factors.
  • Multi-system primary endpoints, weight, HbA1c, liver fat fraction, and cardiovascular biomarkers are being co-primary or key secondary endpoints.
  • MASLD-specific substudies, given glucagon receptor involvement in hepatic fat clearance, liver imaging endpoints are increasingly standard.

Researchers tracking retatrutide clinical trials and retatrutide endpoints will find that these design shifts are already visible in newly registered protocols. The visceral fat research tag aggregates complementary data on adipose tissue outcomes that are increasingly central to these expanded endpoint frameworks.

Safety, the Broader Pipeline, and What Comes Next

Retatrutide's tolerability profile follows the incretin class pattern: nausea, vomiting, and gastrointestinal discomfort are the most common adverse events, with rates generally manageable through dose escalation protocols. The longer trial durations in TRIUMPH-2 and TRIUMPH-3 are generating richer safety datasets than earlier Phase 2 work, including the foundational New England Journal of Medicine Phase 2 publication that first established the compound's potency benchmark.

Safety, the Broader Pipeline, and What Comes Next

Beyond retatrutide itself, the triple agonist concept is catalyzing a broader pipeline shift. Novo Nordisk's UBT251 and other candidates are advancing, and early-stage research is already exploring quadruple and quintuple agonist architectures. The direction is clear: metabolic pharmacology is moving from single-target precision toward multi-receptor orchestration.

For researchers working in adjacent areas, compounds like GLP-3 RT peptide variants and GLP Reta formulations represent the research-grade tools being used to probe these mechanisms at the preclinical level. Those evaluating GLP-3 peptide for sale options should prioritize purity-verified suppliers given the sensitivity of receptor binding studies.

Analyst outlook (speculative, clearly labeled as projections): If TRIUMPH-2 and TRIUMPH-3 read out positively in 2026 to 2027, regulatory submissions are anticipated by late 2027. Analysts broadly expect retatrutide to compete directly with tirzepatide and semaglutide in both obesity and type 2 diabetes indications, potentially capturing significant market share on the basis of superior weight loss magnitude.

Conclusion

The data emerging from Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design is not only advancing a single drug candidate, it is rewriting the rules for how metabolic trials are built. Longer durations, multi-system endpoints, and expanded inclusion criteria are now standard expectations rather than design innovations.

Actionable next steps for researchers and clinicians:

  1. Review the TRIUMPH and TRANSCEND-T2D-1 protocols to understand how multi-system endpoint selection is being operationalized.
  2. Evaluate whether existing study designs in obesity or MASLD research adequately capture hepatic and cardiovascular outcomes alongside weight.
  3. Monitor the broader triple agonist pipeline, UBT251 and emerging quintuple agonist candidates, for design precedents that may inform future protocol development.
  4. Source purity-verified research peptides from reputable suppliers when conducting preclinical receptor studies, ensuring data integrity from the outset.

The metabolic drug paradigm has shifted. Single-receptor thinking is giving way to coordinated multi-target strategies, and the trial infrastructure is following.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-and-glp-3-peptide-research-in-2026-how-triple-agonist-trials-are-res.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-13 13:04:022026-09-13 13:04:02Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design
Page 17 of 81«‹1516171819›»
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top