CJC-1295 With DAC in Longitudinal Studies: Modeling Accumulation, Baseline Drift, and Sparse-Sampling Bias
{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'CJC-1295 With DAC in Longitudinal Studies' centered in crisp white sans-serif on a deep navy semi-transparent panel, 8% safe margins from every edge. Background: a clinical pharmacokinetics laboratory with a glowing multi-line concentration-time curve displayed on a large wall monitor, blue-teal ambient lighting, rows of serum sample vials on a clean bench, editorial medical-journal aesthetic, high contrast, sharp focus.","content":["Annotated mechanism diagram (1536×1024) showing CJC-1295 DAC albumin-binding and drug accumulation over repeated weekly doses: a horizontal timeline with 5 dose events marked as vertical arrows, a rising stepped plasma concentration curve above labeled 'Accumulation Factor', a secondary IGF-1 elevation curve below labeled 'Sustained PD Effect', callout labels: 'Half-life 6-8 days', 'Steady State ~Week 5', 'Carryover Exposure', 'AUC Increase Per Cycle'. White background, teal-and-navy palette, clean clinical-infographic style, all labels inside 5% safe margin, editorial polish.","Numbered four-step flow diagram (1536×1024) illustrating baseline drift in a longitudinal CJC-1295 DAC study: Step 1 labeled 'True Pre-Dose Baseline' shows a flat IGF-1 reference line; Step 2 labeled 'First Injection, IGF-1 Rises' shows an upward curve; Step 3 labeled 'Mid-Study Pre-Dose Measurement' shows a falsely elevated reference point with a red callout 'Drift Error'; Step 4 labeled 'Underestimated Drug Effect' shows a compressed apparent response. Warm amber-and-charcoal palette, clean sans-serif labels, clinical diagram style, all text inside safe margins, 1536×1024 landscape format.","Split-panel annotated editorial graphic (1536×1024) contrasting dense vs. sparse pharmacokinetic sampling schedules for a long-acting peptide: left panel labeled 'Dense Sampling' shows a smooth concentration-time curve with 12 evenly spaced data points and callout 'Accurate Terminal Half-Life'; right panel labeled 'Sparse Sampling' shows only 3 data points on the same curve with callouts 'Missed Late Phase', 'Overestimated Clearance', 'Inter-Individual Variability Hidden'. Deep burgundy and slate-blue palette, clean infographic layout, thin dividing line between panels, all labels 1-5 words inside 5% safe margin, editorial medical-research style."]

Fewer than six weeks of published human exposure data exist for CJC-1295 with DAC, yet researchers routinely extrapolate its pharmacokinetics across multi-month protocols. That gap between available evidence and real-world application is exactly why understanding CJC-1295 with DAC in longitudinal studies: modeling accumulation, baseline drift, and sparse-sampling bias has become a critical methodological concern in 2026.
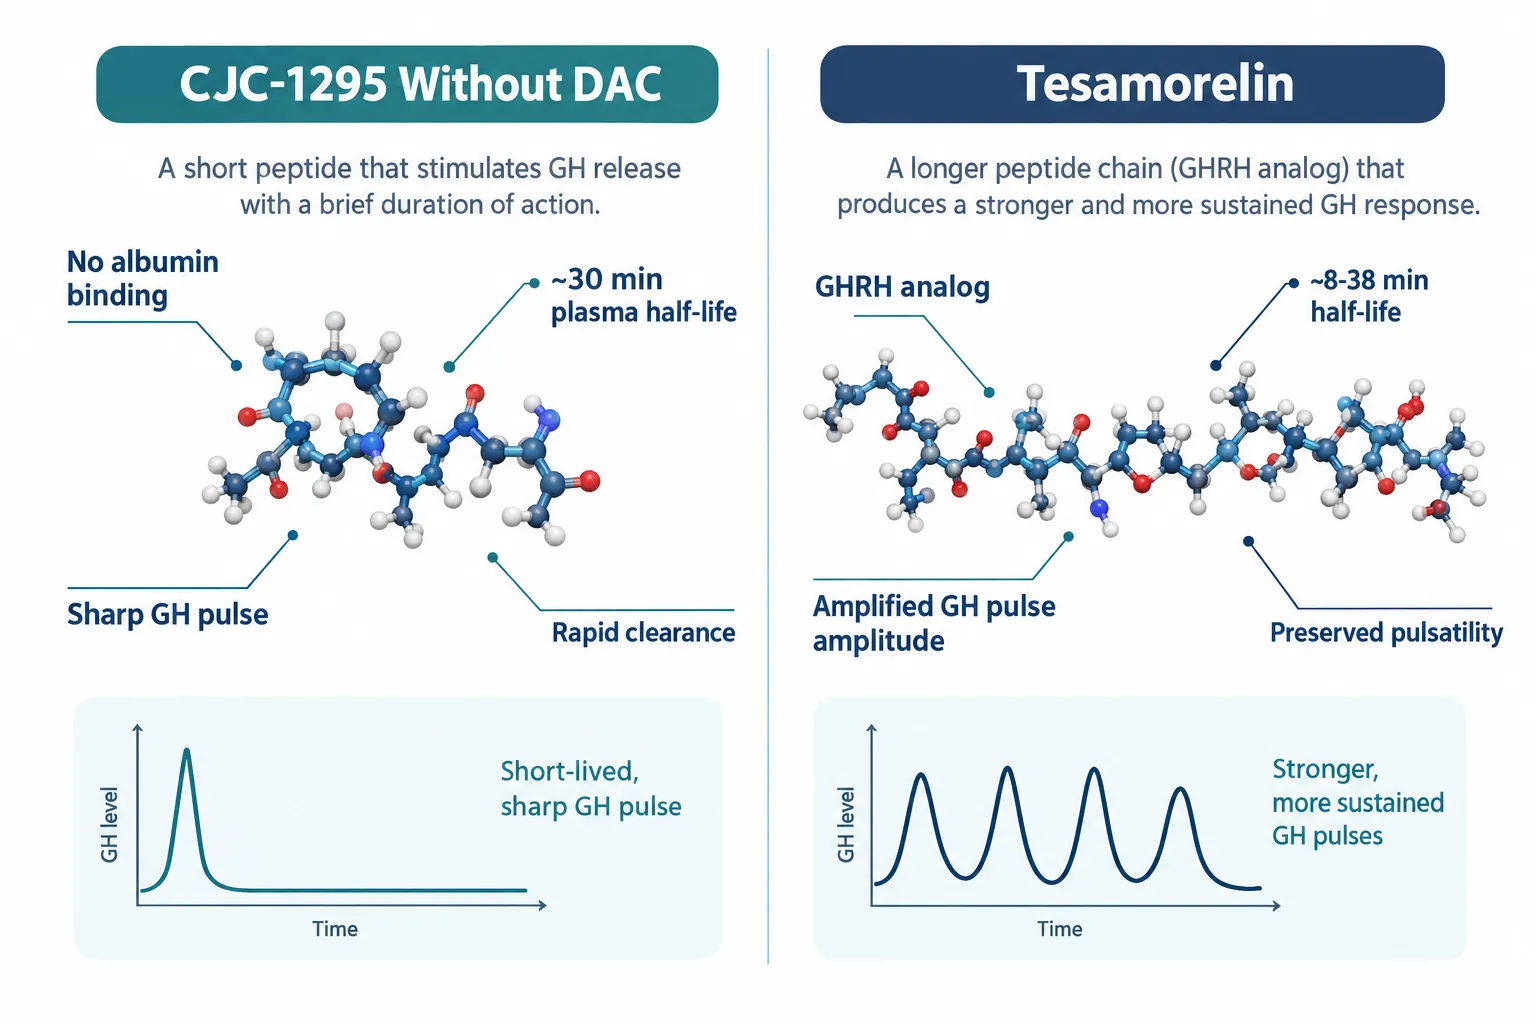
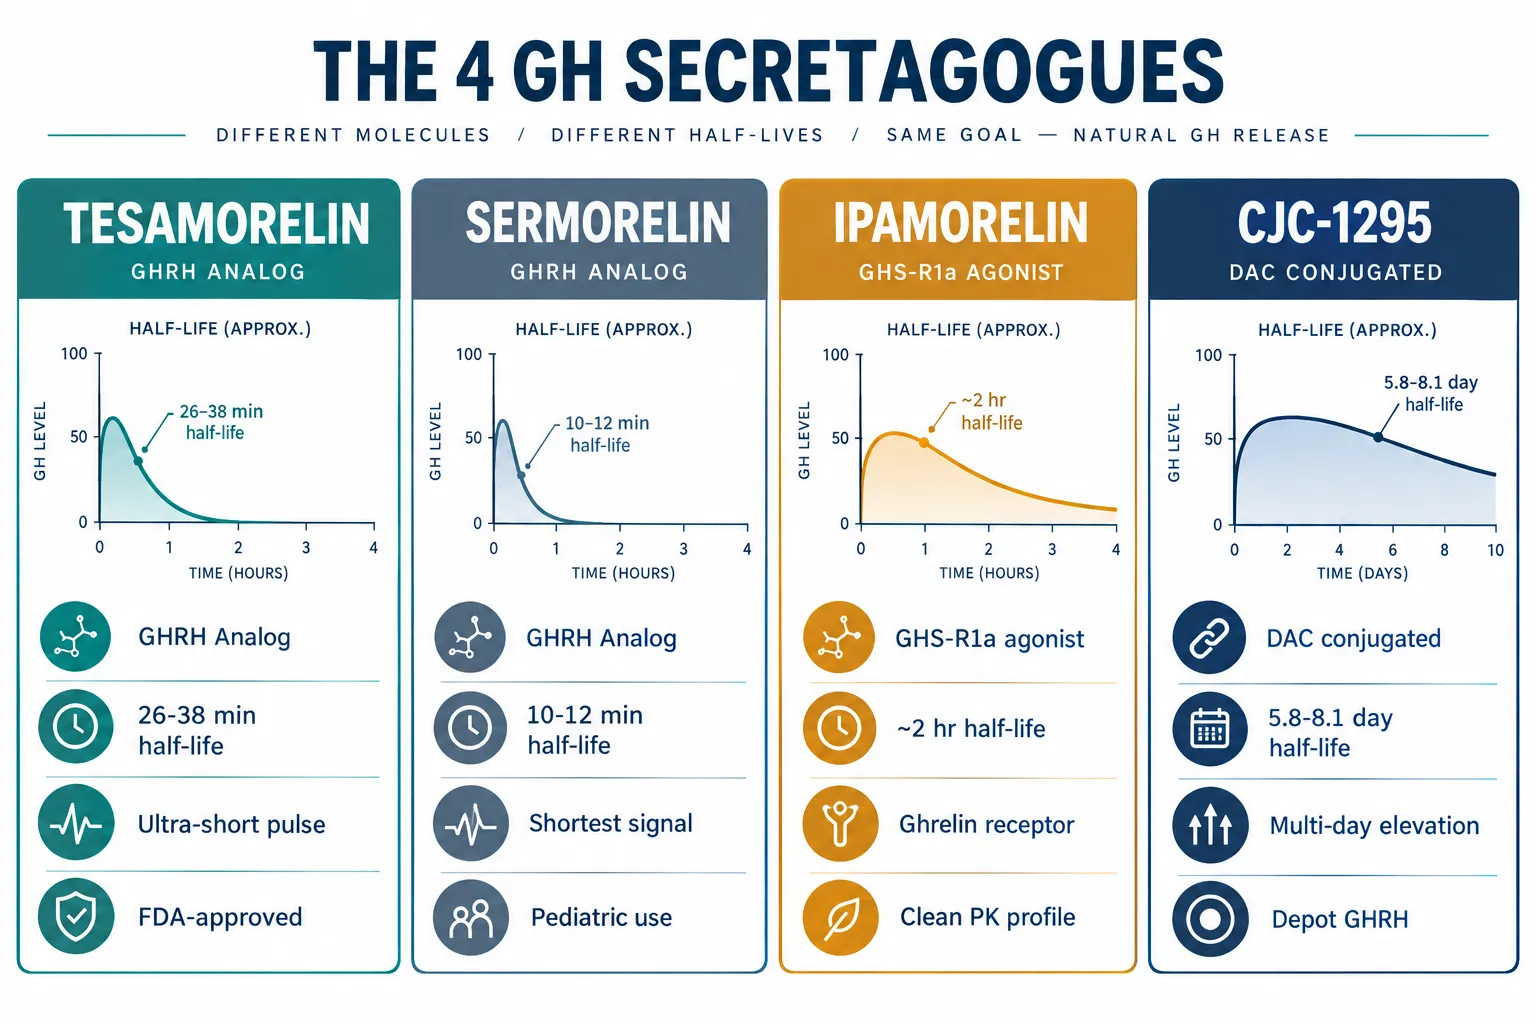
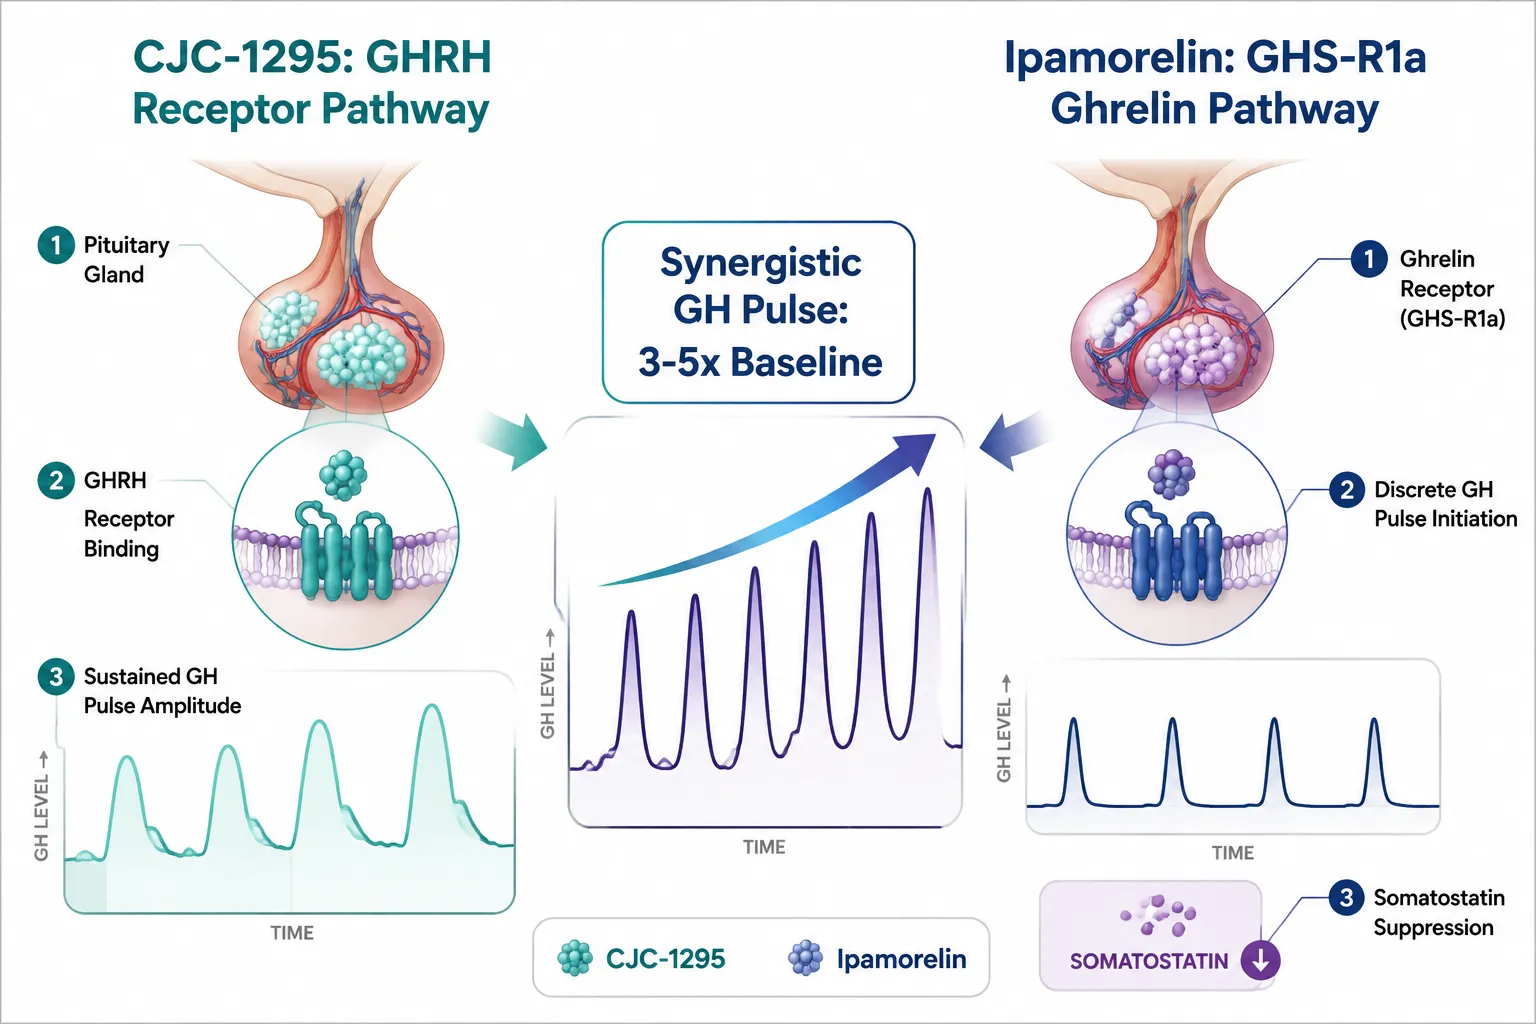
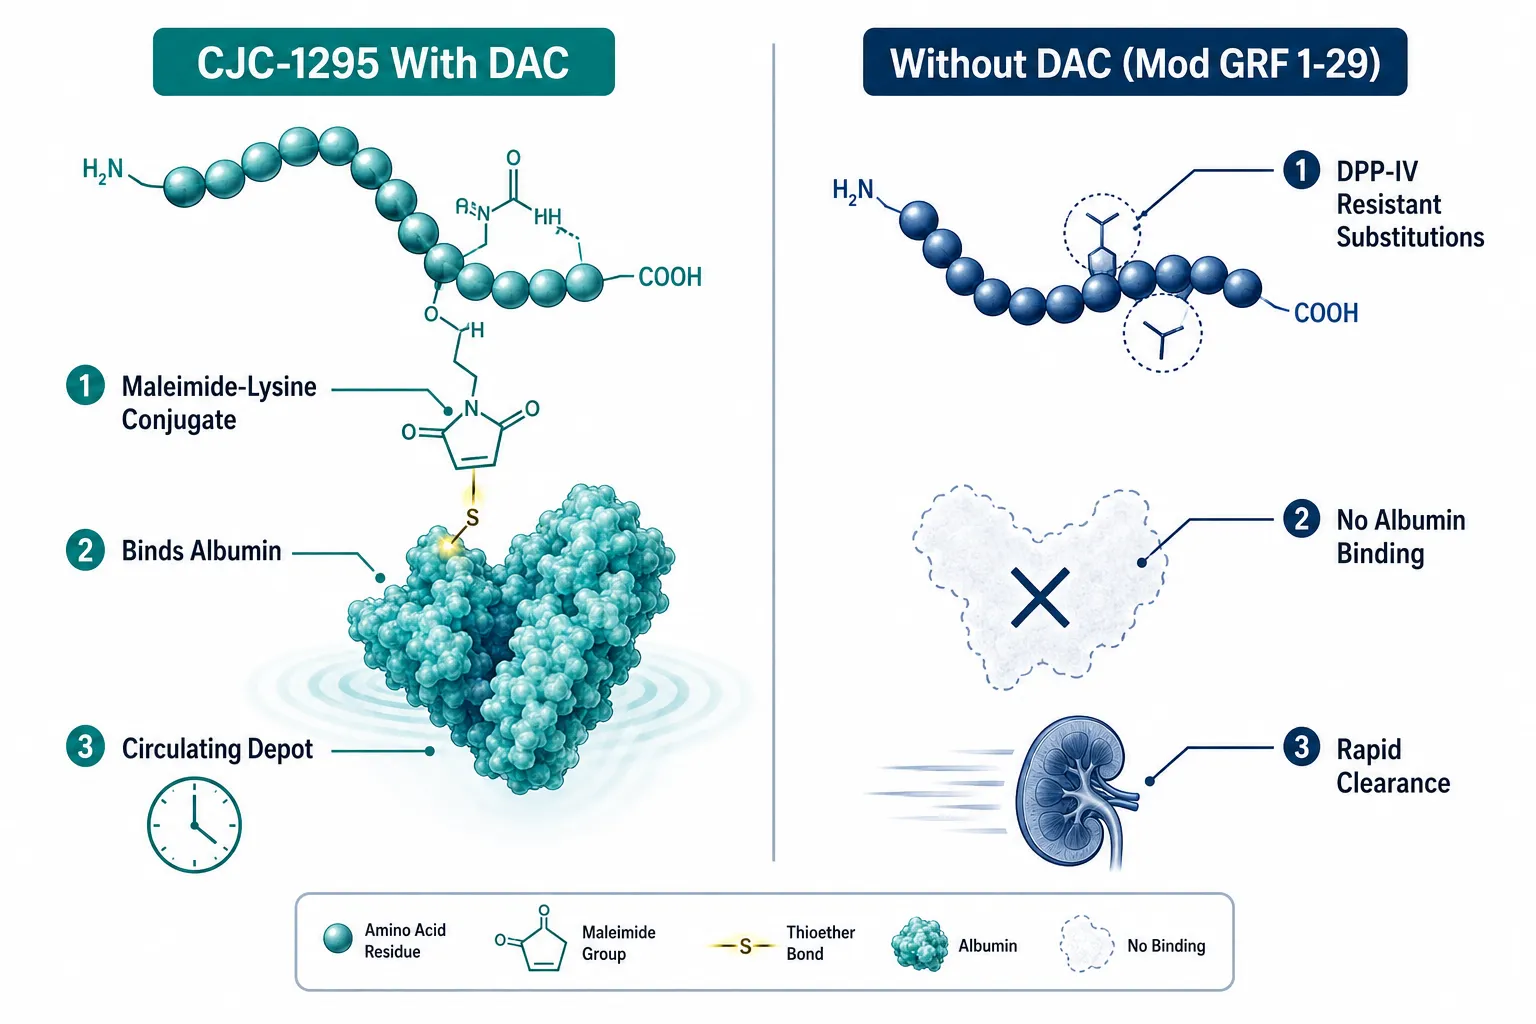
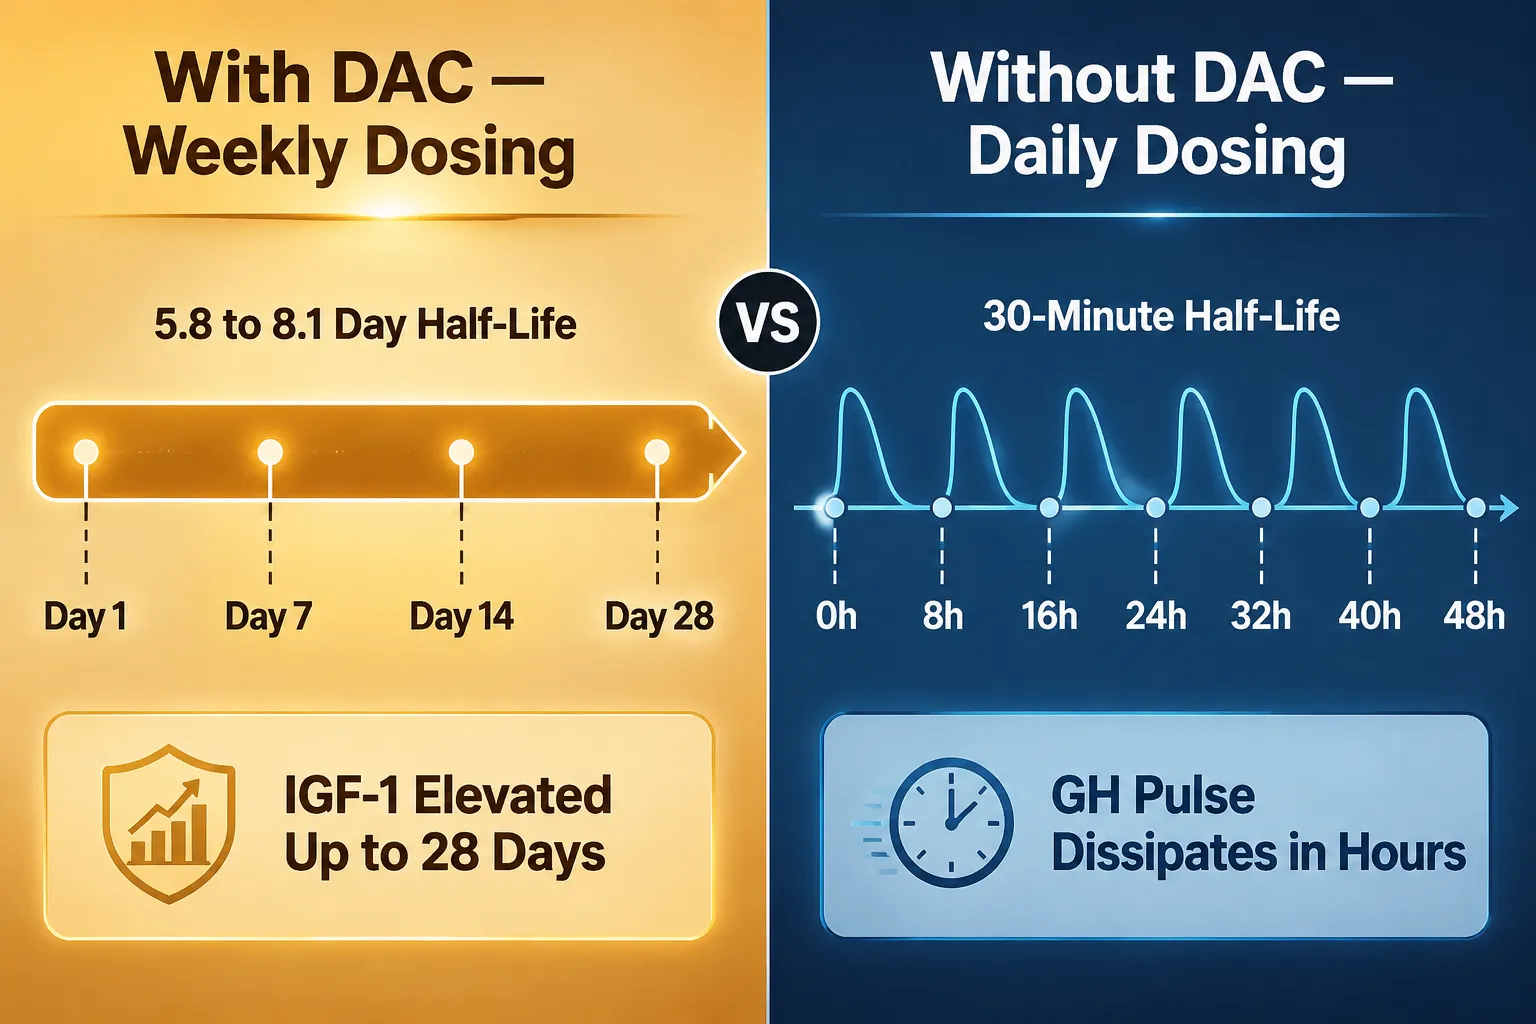
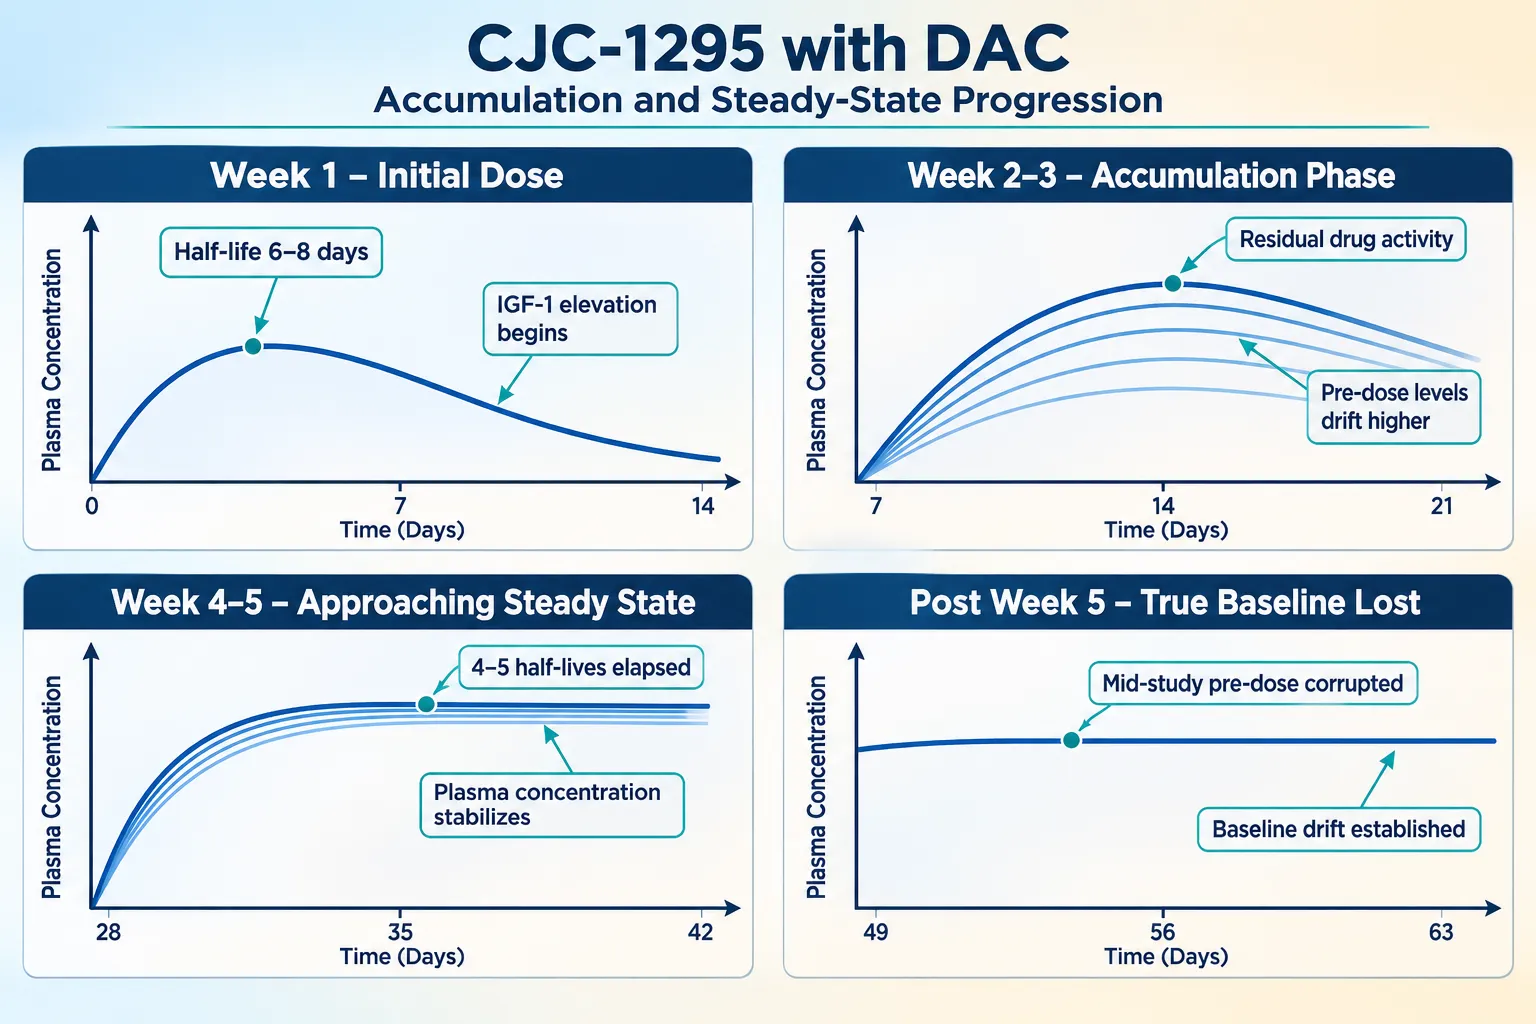
The peptide's defining feature, covalent albumin binding via a reactive succinimide moiety, extends its half-life from roughly 30 minutes (for non-DAC analogs) to an estimated 6-8 days in healthy adults. That extended residence time creates compounding design problems in repeat-exposure studies that are easy to overlook and difficult to correct after data collection.
Key Takeaways
- CJC-1295 with DAC has a human half-life of approximately 6-8 days, producing measurable accumulation under weekly dosing schedules.
- Steady-state plasma concentrations are not reached until approximately 4-5 half-lives have passed, roughly four to five weeks into a protocol.
- Mid-study "pre-dose" IGF-1 measurements are not true baselines; they already reflect prior drug exposure, a phenomenon called baseline drift.
- Sparse pharmacokinetic sampling in the original Phase I/II trials limits the precision of the 6-8 day half-life estimate and masks inter-individual variability.
- Future longitudinal trials should model accumulation curves explicitly, establish drug-free baselines before first exposure, and use sufficiently dense sampling across multiple dose cycles.
Why Accumulation Defines the Longitudinal Pharmacokinetics of CJC-1295 With DAC
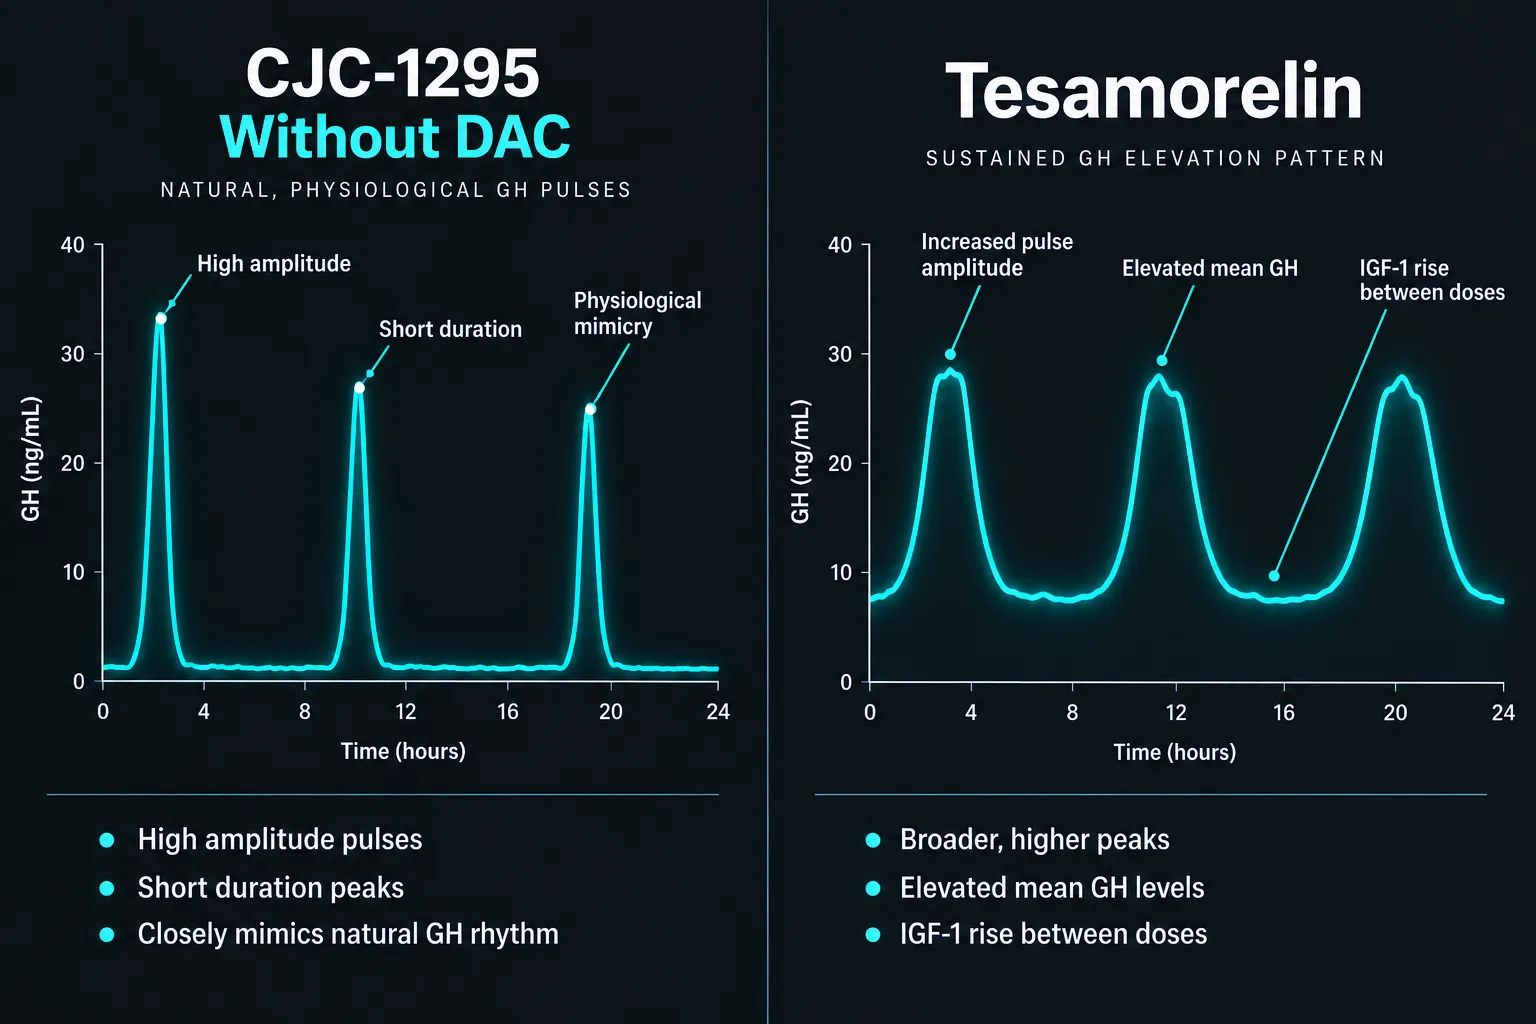
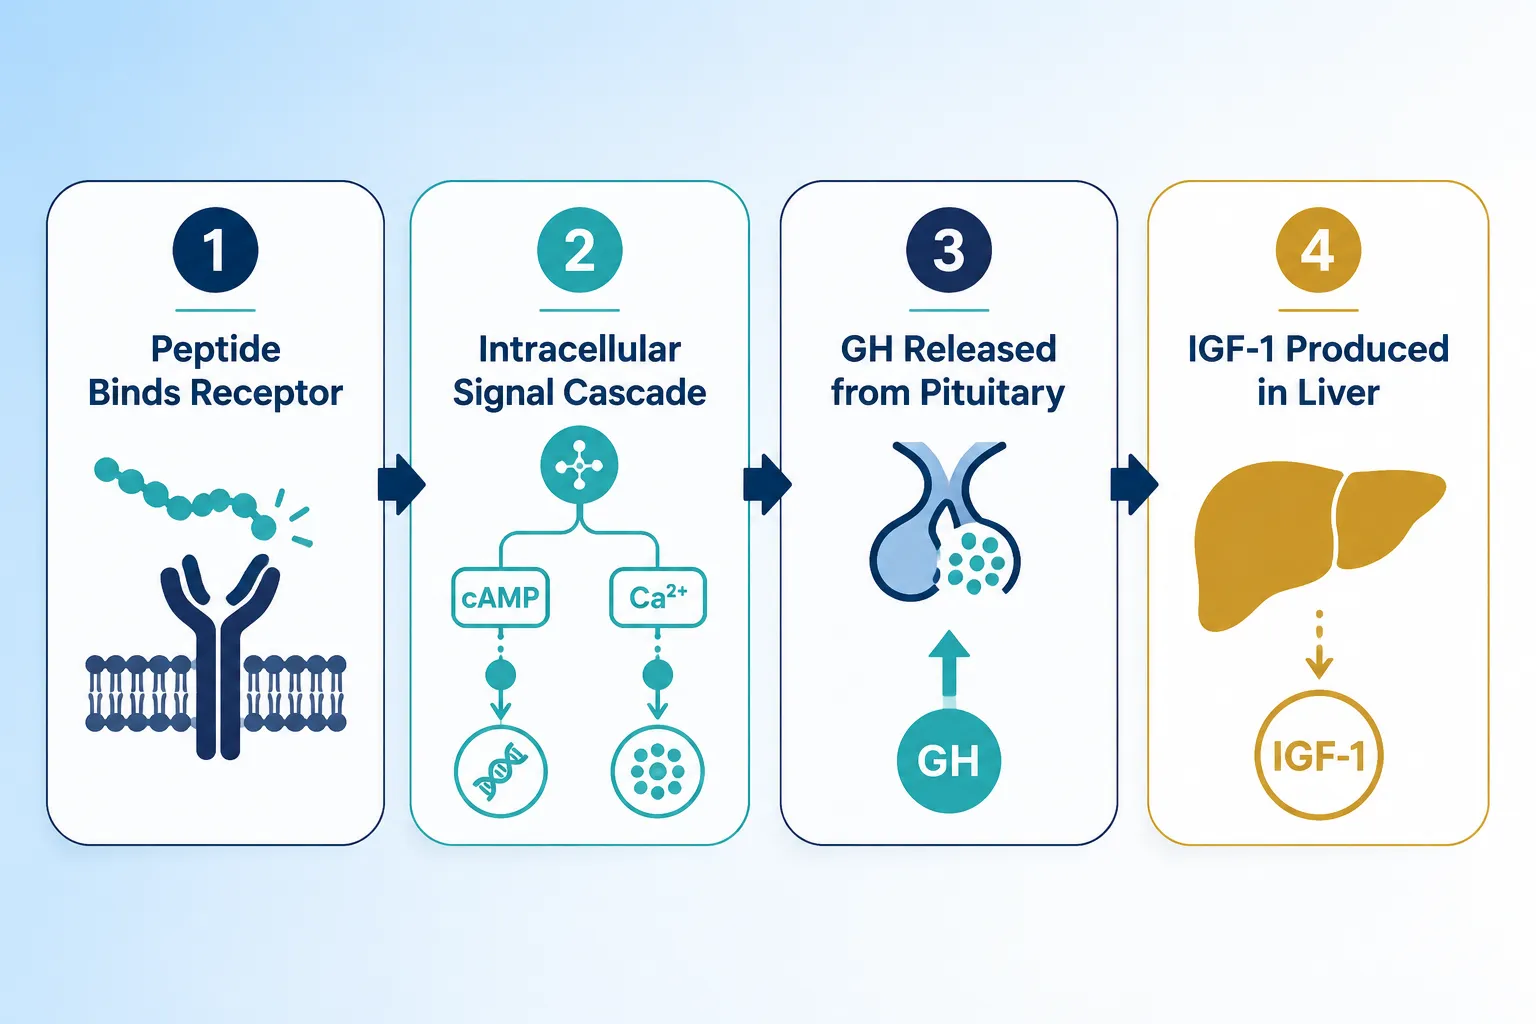
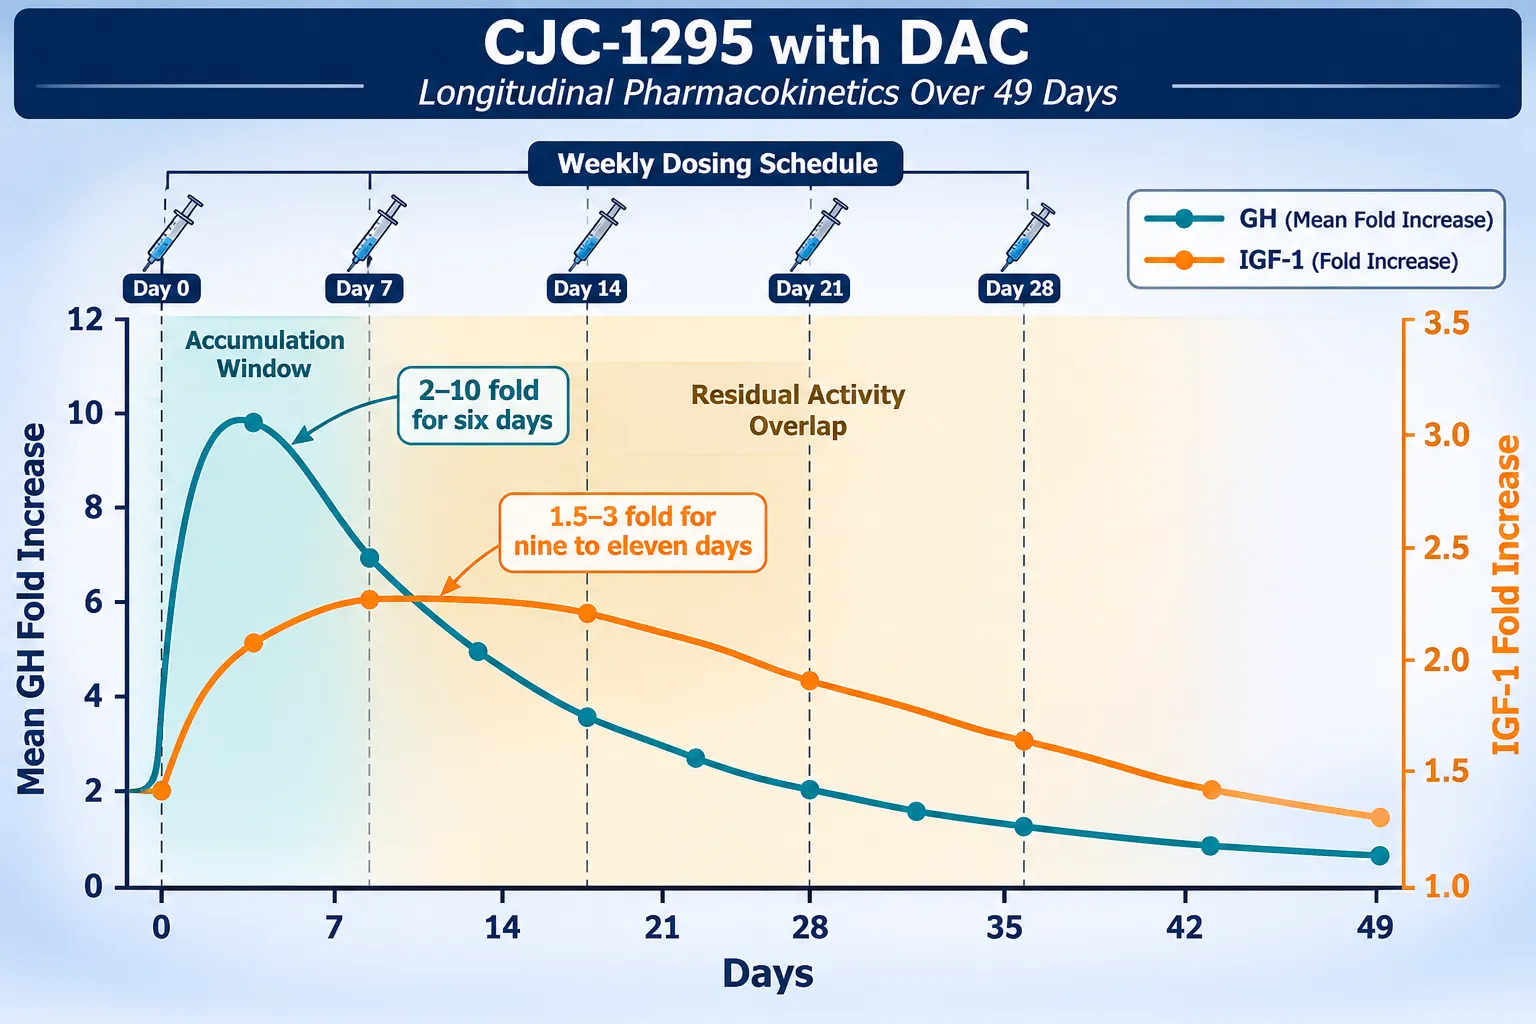
A single injection of CJC-1295 with DAC elevates mean growth hormone roughly 2-10 fold for at least six days, and IGF-1 by approximately 1.5-3 fold for nine to eleven days. Those numbers come from the foundational ConjuChem Phase I/II program, which included a 28-day single-exposure study and a 49-day repeat-exposure study in healthy adults.
What those summary statistics do not immediately communicate is what happens across multiple doses.
The accumulation math is straightforward:
| Half-lives elapsed | Approximate % of Steady State reached |
|---|---|
| 1 | 50% |
| 2 | 75% |
| 3 | 88% |
| 4 | 94% |
| 5 | 97% |
With a 6-8 day half-life, steady state under weekly dosing arrives only after four to five weeks. This means that by the third or fourth dose, peak plasma concentrations (Cmax) and total exposure (AUC) are meaningfully higher than after the first injection, not because the dose changed, but because drug from earlier cycles has not yet cleared.
For researchers planning or interpreting multi-week protocols, this has direct consequences. A participant evaluated at week six is not experiencing the same pharmacological signal as one evaluated at week one, even under identical dosing. Any longitudinal analysis that treats each cycle as independent will mischaracterize the exposure-response relationship.
This distinction also matters when comparing CJC-1295 with DAC to shorter-acting analogs. For background on how this peptide fits into broader GHRH-analog protocols, the sermorelin vs CJC-1295 overview provides useful framing. For combined-protocol assay considerations, the CJC-1295 Ipamorelin assay planning and sourcing checklist is a practical resource.
Baseline Drift: How Prior Exposure Corrupts Mid-Study Reference Points
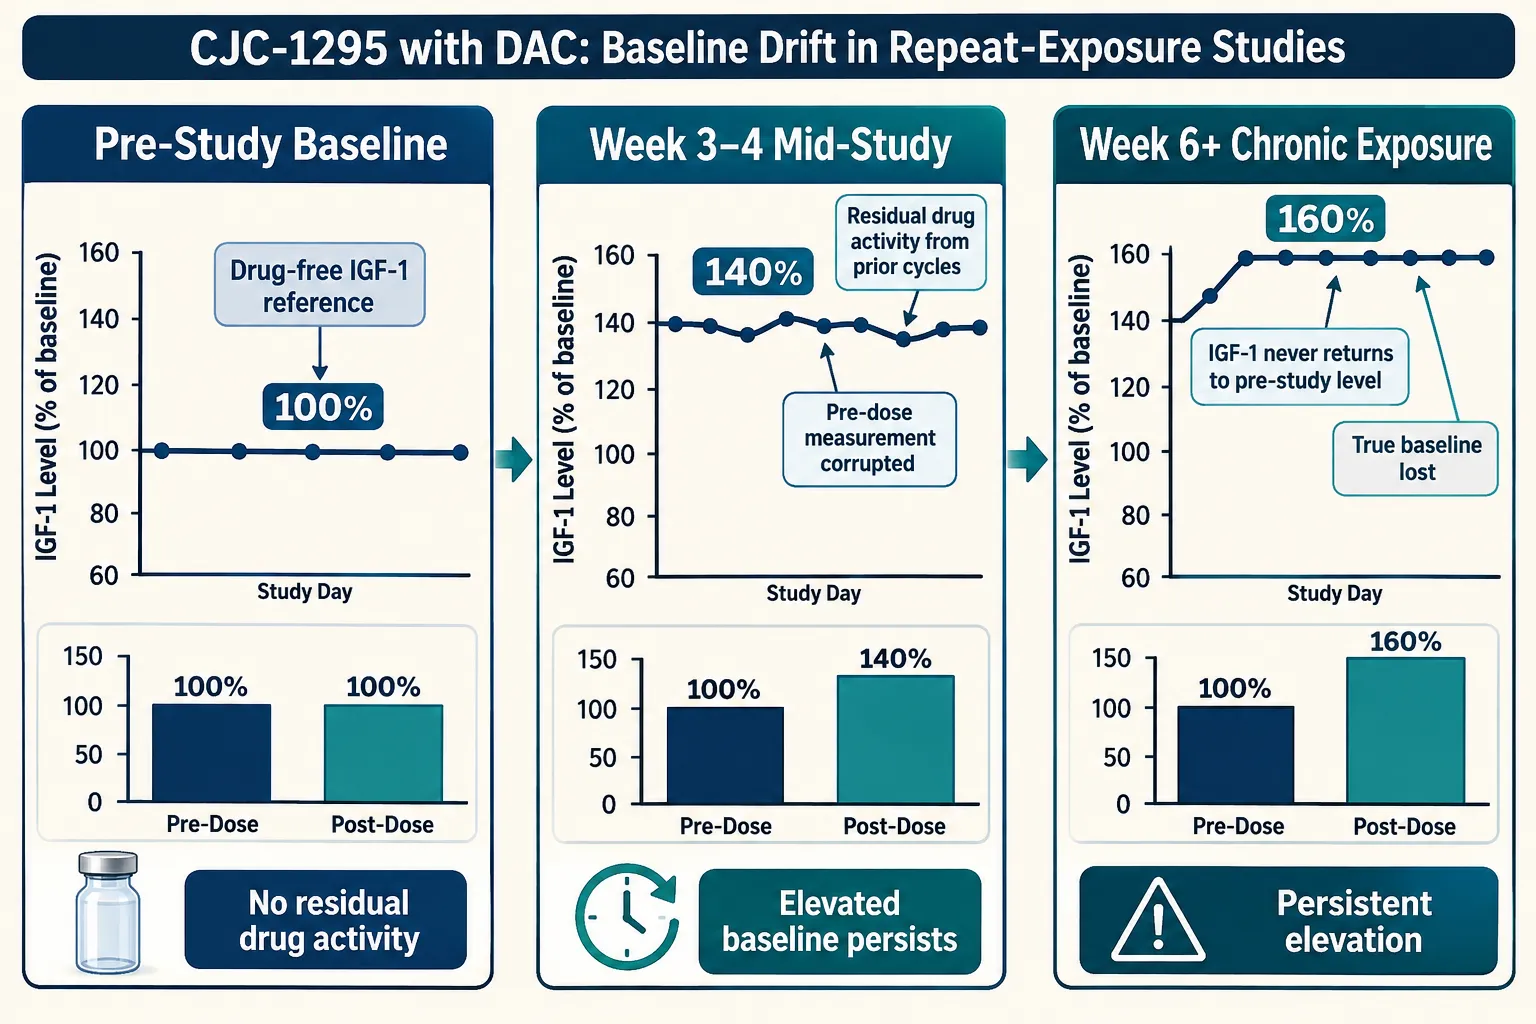
One of the most consequential issues in CJC-1295 with DAC longitudinal studies is baseline drift, the progressive upward shift of pre-dose hormone measurements caused by residual drug activity from previous cycles.
In the repeat-exposure Phase I/II data, mean IGF-1 never fully returned to pre-study values within the 49-day observation window. That single finding reframes every "pre-dose" blood draw taken after the first injection: those measurements are not baselines. They are residual pharmacodynamic states.
"Using a mid-study pre-dose IGF-1 value as a true baseline underestimates the drug's effect and misrepresents the trajectory back to physiological norm."
The practical consequences include:
- Underestimated drug effect: If the apparent "baseline" is already elevated, the measured response looks smaller than it actually is.
- False plateau interpretation: A flat IGF-1 curve late in a study may indicate stable supra-physiological elevation, not return to normal.
- Misleading safety signal interpretation: Elevated IGF-1 at the end of a study may be misclassified as a stable new normal rather than persistent pharmacodynamic effect.
Correcting for baseline drift requires establishing a true drug-free baseline before the first exposure and then modeling subsequent pre-dose values as dependent pharmacodynamic endpoints, not independent reference points. Studies that do not pre-specify this design element are largely unable to separate drug carryover from biological variability after the fact.
Dosing context matters here as well. Resources such as the sermorelin, ipamorelin, and CJC-1295 combination overview and the ipamorelin CJC-1295 dosage reference illustrate how stacked protocols compound this drift problem across multiple long-acting agents simultaneously.
Sparse-Sampling Bias and What the Phase I/II Data Cannot Tell Us
The third methodological pillar of CJC-1295 with DAC in longitudinal studies: modeling accumulation, baseline drift, and sparse-sampling bias concerns how the foundational pharmacokinetic parameters were derived.
Intensive concentration-time sampling in the original trials was conducted only in subsets of participants and at limited timepoints. Later-cycle data, the very data needed to characterize accumulation, were not uniformly collected across all subjects. The widely cited 6-8 day half-life estimate emerged from combining these partial profiles into a single composite, which carries several risks:
- Inter-individual variability is obscured. Participants with faster or slower albumin turnover may accumulate drug at substantially different rates, but sparse group-level averaging hides this.
- Terminal elimination is poorly characterized. The late portion of the concentration-time curve, the segment that determines true half-life, is the hardest to capture with limited sampling windows.
- Extrapolation to off-label regimens is unreliable. Twice-weekly dosing, common outside clinical trial settings, would increase accumulation substantially compared to weekly dosing, but no published data model this scenario adequately.
FDA educational materials filed under a 2024 docket and updated through mid-2025 acknowledge that CJC-1295 with DAC produces rising peak concentrations under repeated dosing and explicitly flag concerns about its long-acting profile in the context of unregulated compounding and unsupervised use.
Critically, a larger study of approximately 192 participants was reportedly conducted but never published. That gap leaves current modeling efforts dependent on short-term Phase I/II data extrapolated over longer time horizons, a recognized limitation that researchers must account for explicitly rather than ignore.
Methodological Recommendations for Future Longitudinal Protocols
Any future study design involving CJC-1295 with DAC should address the following elements before data collection begins:
- Pre-exposure baseline window: Collect hormone data for at least 7-10 days before first dosing to establish a drug-free reference.
- Explicit accumulation modeling: Report accumulation factor and estimated steady-state Cmax across dose cycles, not only first-dose PK.
- Dense sampling across multiple cycles: Include rich concentration-time data from at least the first, third, and fifth dose cycles to capture both early and steady-state kinetics.
- Individual-level PK analysis: Avoid relying solely on mean group profiles; mixed-effects modeling preserves inter-individual information that group averaging destroys.
- Defined washout period: End-of-study follow-up should extend at least 4-5 half-lives (roughly 30-40 days) beyond the last dose to characterize true return to baseline.
For compound-specific preparation context, the tesa, CJC-1295, and ipamorelin 12 mg blend dosing guide and the blend reconstitution reference offer relevant technical grounding for researchers working with multi-peptide formats.
Conclusion
The phrase "CJC-1295 with DAC in longitudinal studies: modeling accumulation, baseline drift, and sparse-sampling bias" is not merely an academic label, it is a practical checklist of the three most common ways that long-duration protocols misread this peptide's pharmacological signal.
Actionable next steps for researchers and clinicians in 2026:
- Never treat a mid-study pre-dose hormone measurement as a true baseline; design for a drug-free pre-exposure period.
- Build accumulation curves into the analysis plan before the first participant is dosed.
- Acknowledge the 6-8 day half-life estimate as derived from sparse, subset-level data and design sampling schedules that can challenge or refine it.
- Treat the longest published continuous human exposure (49 days) as the boundary of evidence, and label anything beyond it as extrapolation.
The data needed to fully characterize this compound's longitudinal behavior in humans largely do not yet exist in the published literature. Recognizing that gap, and designing around it, is the most important thing any research team can do before beginning a multi-week CJC-1295 with DAC protocol.