Seroquel (Quetiapine) Confounding Metrics in Metabolic Studies: Isolating GLP-3 Retatrutide Weight Loss Signatures
{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Seroquel (Quetiapine) Confounding Metrics' in crisp white sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge, two lines balanced in length, no character touches the edge. Background: split editorial composition showing a molecular receptor diagram on the left blending into a clinical metabolic data chart on the right, teal and deep blue color palette, medical research laboratory aesthetic, high-contrast editorial quality, magazine cover polish, bright studio lighting.","content":["Annotated mechanism-of-action diagram (1536×1024) showing quetiapine metabolic pathway disruption in a clinical research context. Three labeled panels side by side: Panel 1 labeled 'Weight Gain Pathway' showing H1/5-HT2C receptor blockade with callout lines to 'Hyperphagia', 'Insulin Resistance', 'Dyslipidemia'; Panel 2 labeled 'Metabolic Markers Affected' with callout labels 'Fasting Glucose', 'BMI Shift', 'Triglycerides', 'Leptin Dysregulation'; Panel 3 labeled 'Confounding Risk Level' with a simple graduated scale from Low to High. Teal-navy-white palette, clean white background, editorial medical-research style, sharp callout lines, labels 1-5 words each inside safe margins.","Split-screen editorial infographic (1536×1024) comparing GLP-3 retatrutide weight-loss signature isolation. Left half labeled 'With Quetiapine Confounder' showing a cluttered metabolic signal graph with overlapping lines, annotations 'Masked Fat Loss', 'Inflated Baseline BMI', 'Hyperphagic Offset'; right half labeled 'Controlled Study Design' showing a clean descending weight-loss curve with callouts 'True Fat Mass Reduction', 'Lean Mass Preserved', 'Triple Agonist Signal Isolated'. Bright clinical white background, warm amber vs cool teal color contrast between panels, bold dividing line center, medical data-visualization aesthetic, editorial quality.","Numbered step-by-step process flow diagram (1536×1024) for designing metabolic studies that isolate retatrutide efficacy from antipsychotic confounders. Five horizontal steps with connecting arrows: Step 1 'Screen for Quetiapine Use' with sub-label 'Dose and Duration Log'; Step 2 'Stratify by Antipsychotic Load' with sub-label 'Low vs High Exposure Groups'; Step 3 'Establish Metabolic Baseline' with sub-label 'Glucose, Lipids, BMI, MASLD Score'; Step 4 'Apply Statistical Controls' with sub-label 'Covariate Adjustment Models'; Step 5 'Isolate GLP-3 Signature' with sub-label 'Fat Mass vs Lean Mass Delta'. Deep navy background, teal accent arrows, white label boxes, bold step numbers in amber circles, editorial clinical research aesthetic, sharp and legible."]
Roughly one in five patients prescribed quetiapine for off-label conditions such as insomnia or anxiety gains more than 7% of their baseline body weight within the first year of treatment. When those same patients enter a retatrutide clinical trial, that pre-existing metabolic burden does not disappear, it hides inside the data. Addressing Seroquel (Quetiapine) confounding metrics in metabolic studies: isolating GLP-3 retatrutide weight loss signatures is therefore not a statistical nicety but a research imperative if clinicians are to trust what they see in the weight-loss curves.
Key Takeaways
- Quetiapine causes dose-dependent weight gain, insulin resistance, and dyslipidemia that directly contaminate metabolic outcome data.
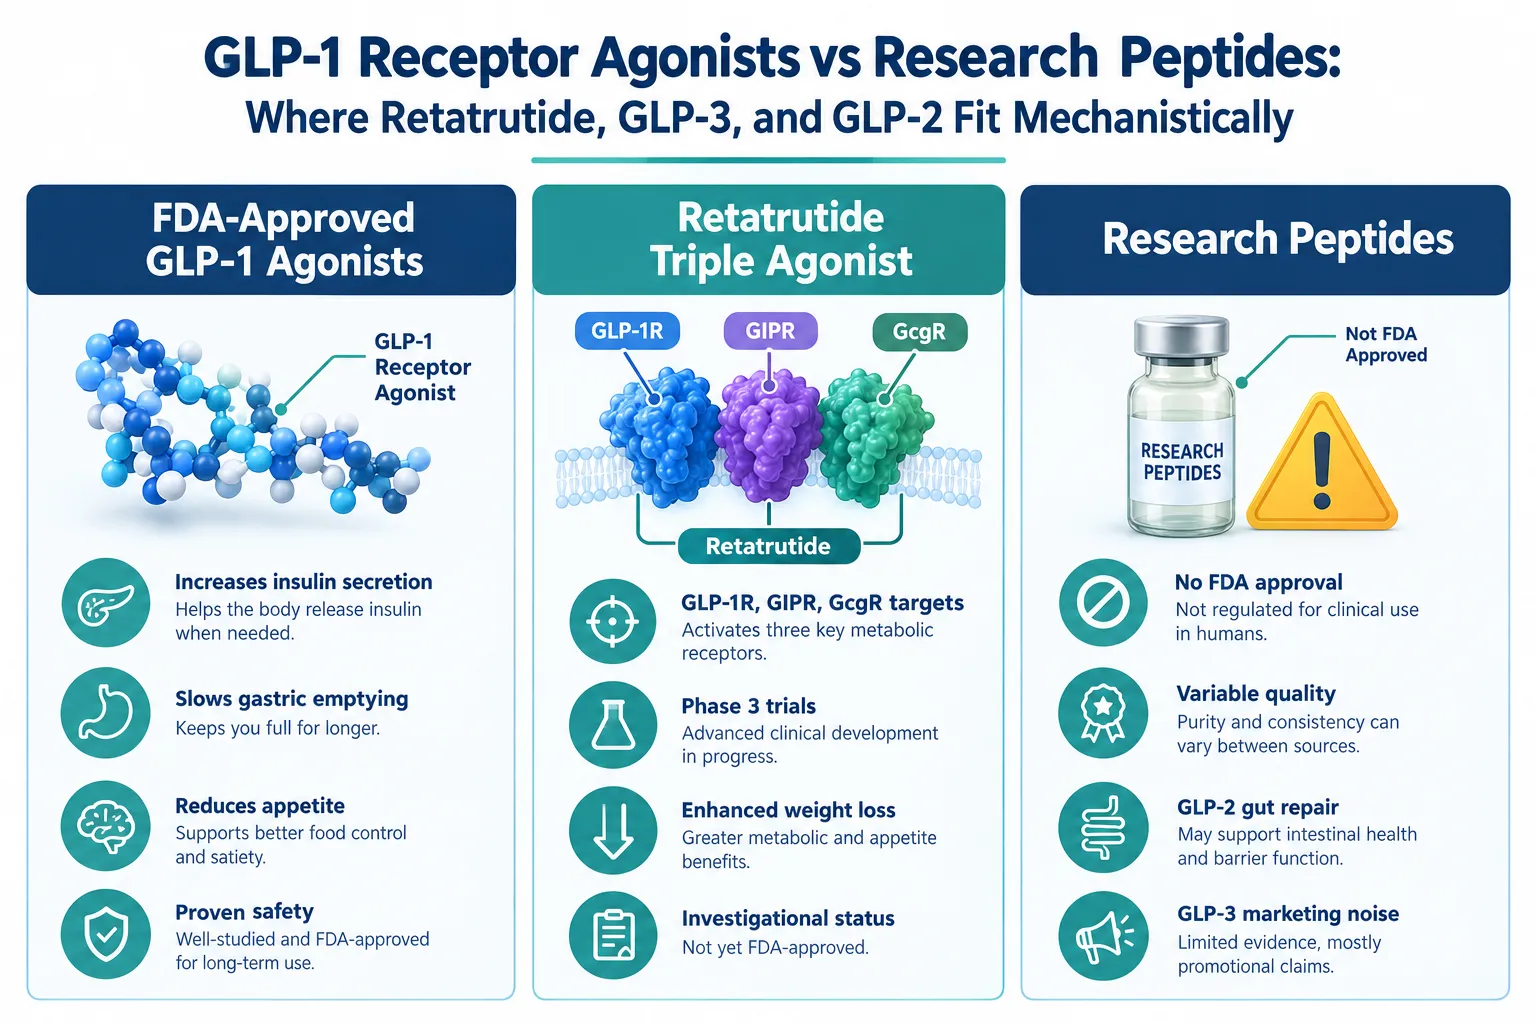
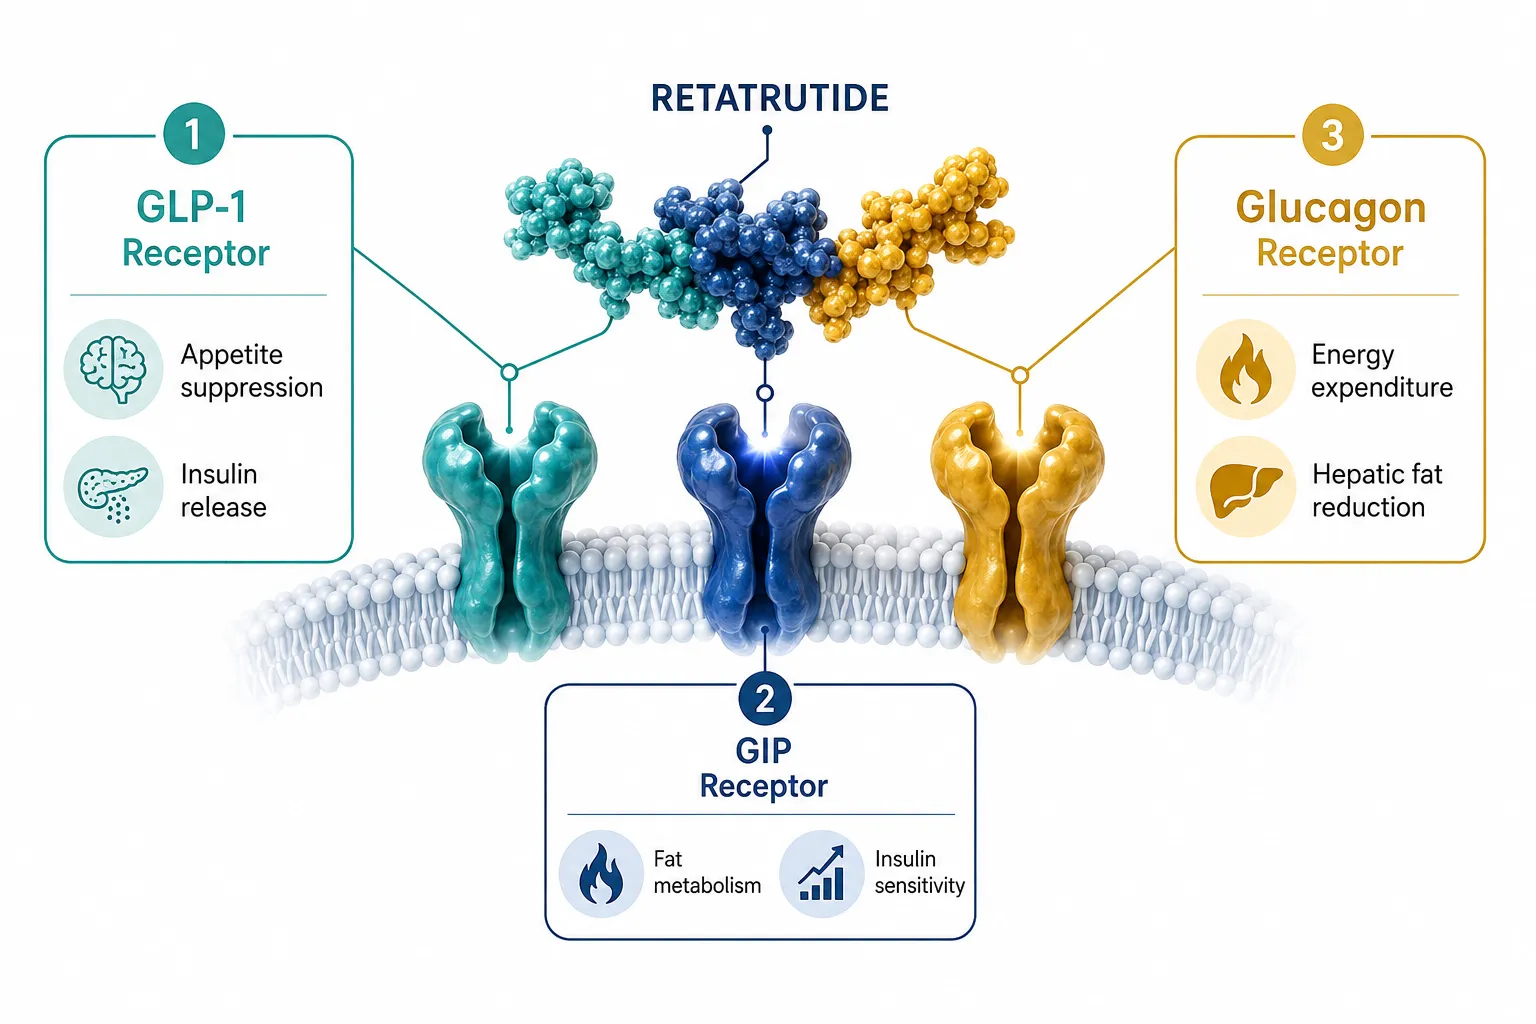
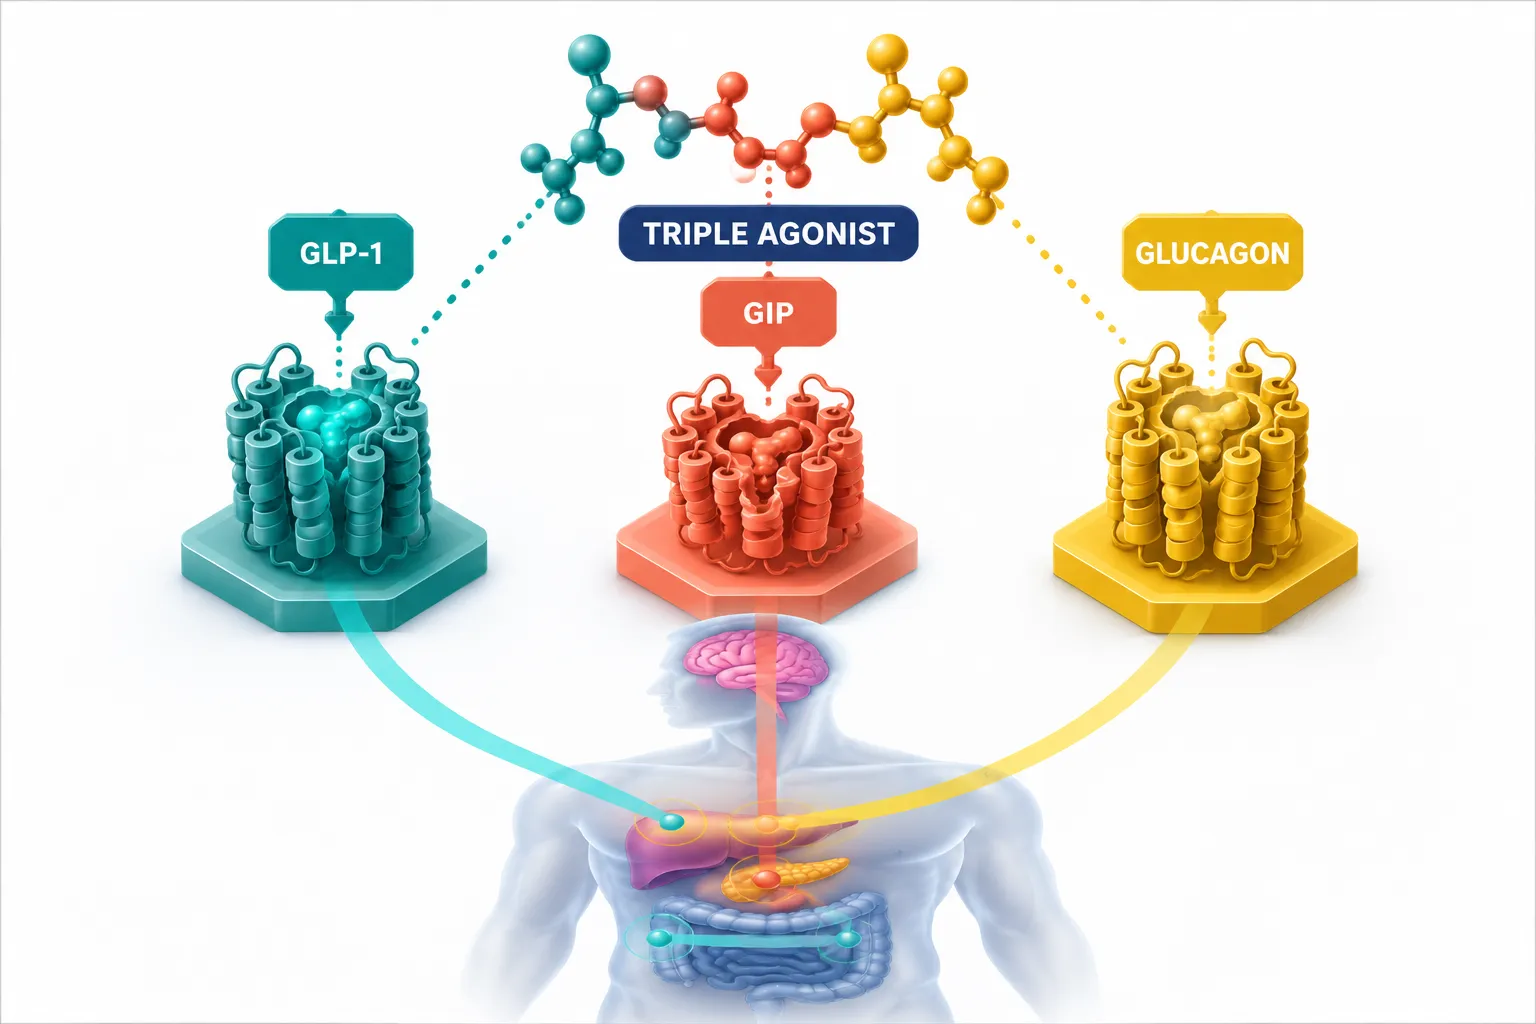
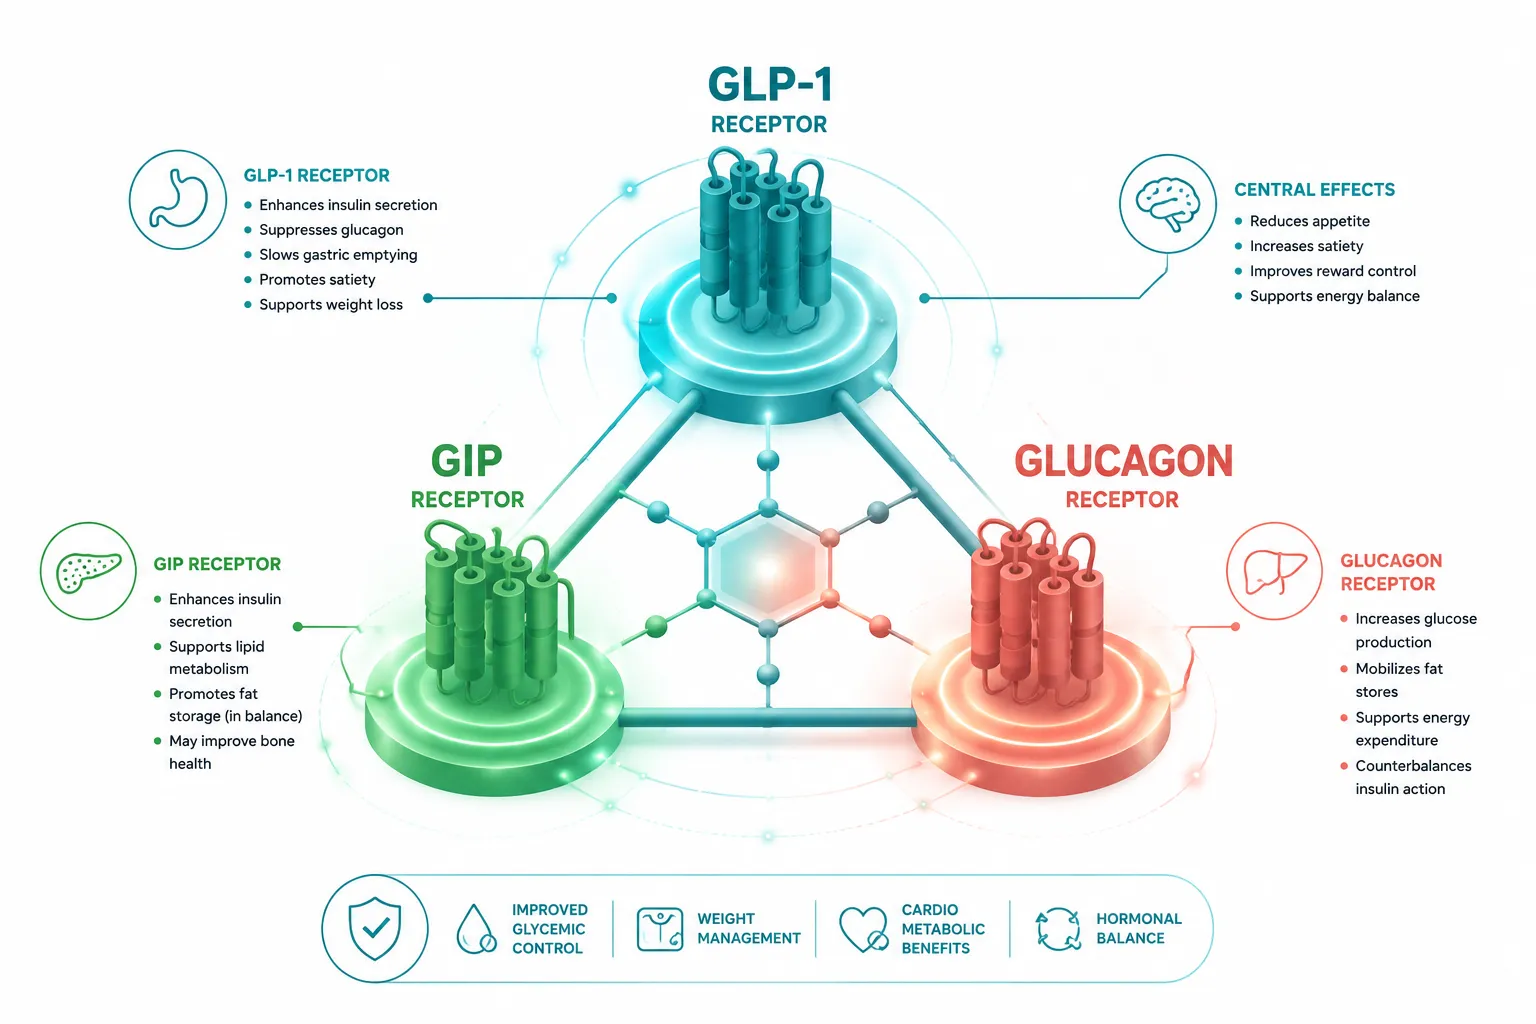
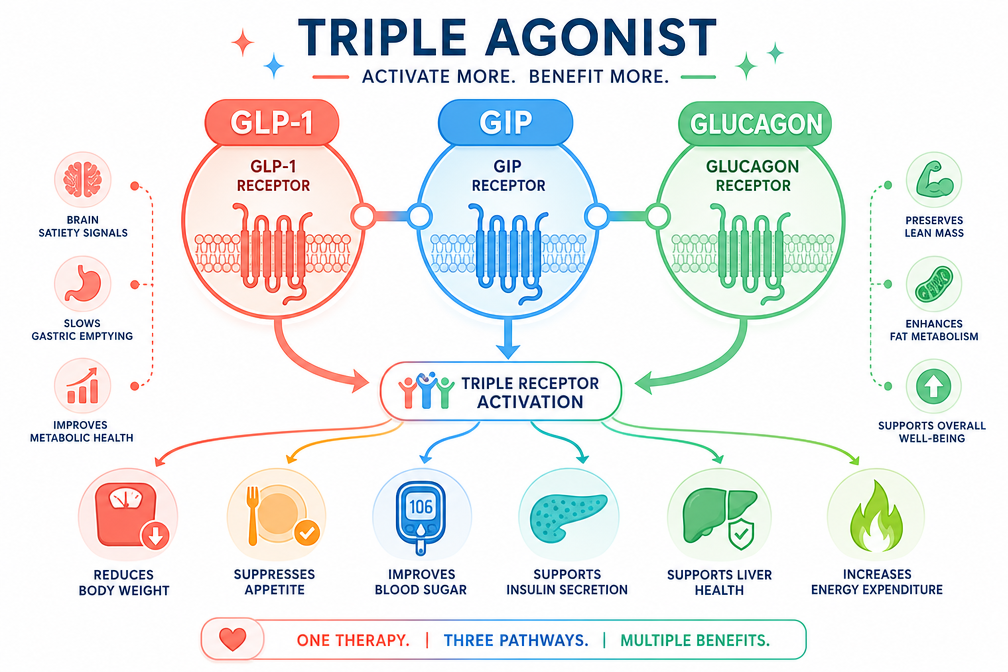
- Retatrutide, a GLP-1/GIP/glucagon triple agonist, produces a distinct fat-preferential weight-loss signature that can be masked by antipsychotic-induced hyperphagia.
- Failure to screen and stratify for quetiapine use inflates baseline BMI and distorts the apparent magnitude of GLP-3 efficacy.
- Children and adolescents are disproportionately vulnerable to quetiapine metabolic side effects, making pediatric subgroup analysis especially error-prone.
- Rigorous covariate adjustment and stratified randomization are the two highest-yield corrective strategies.
How Quetiapine Disrupts Metabolic Baselines
Quetiapine's metabolic profile is driven by its antagonism of histamine H1 receptors and serotonin 5-HT2C receptors. Both of these receptor interactions promote appetite dysregulation, reduce satiety signaling, and encourage fat accumulation, particularly visceral fat. The result is a distinct pattern of antipsychotic-induced metabolic dysfunction that includes:
- Weight gain: Averaging 2-5 kg in short-term studies; substantially more with chronic use.
- Insulin resistance: Elevated fasting glucose and HOMA-IR scores, independent of weight change.
- Dyslipidemia: Elevated triglycerides and reduced HDL cholesterol.
- Leptin dysregulation: Altered adipokine signaling that obscures true energy balance.
Prospective cohort data confirm that these effects are dose-dependent. Patients on higher doses show faster and more pronounced shifts across every metabolic marker compared to those on low-dose regimens. Off-label use at lower doses does not confer immunity, even sub-therapeutic doses used for sleep produce measurable glucose and lipid changes over months.
Pediatric populations deserve special attention here. Children and adolescents demonstrate heightened vulnerability to quetiapine-induced metabolic shifts, with greater relative weight gain per milligram of exposure than adults. Any metabolic study that includes younger participants without stratifying for antipsychotic use is at particular risk of biased endpoints.
Key insight: A participant entering a retatrutide trial with two years of quetiapine exposure does not share the same metabolic starting point as a drug-naive control, even if their baseline BMI appears identical on paper.
The Retatrutide Weight-Loss Signature and Why It Is Vulnerable to Noise
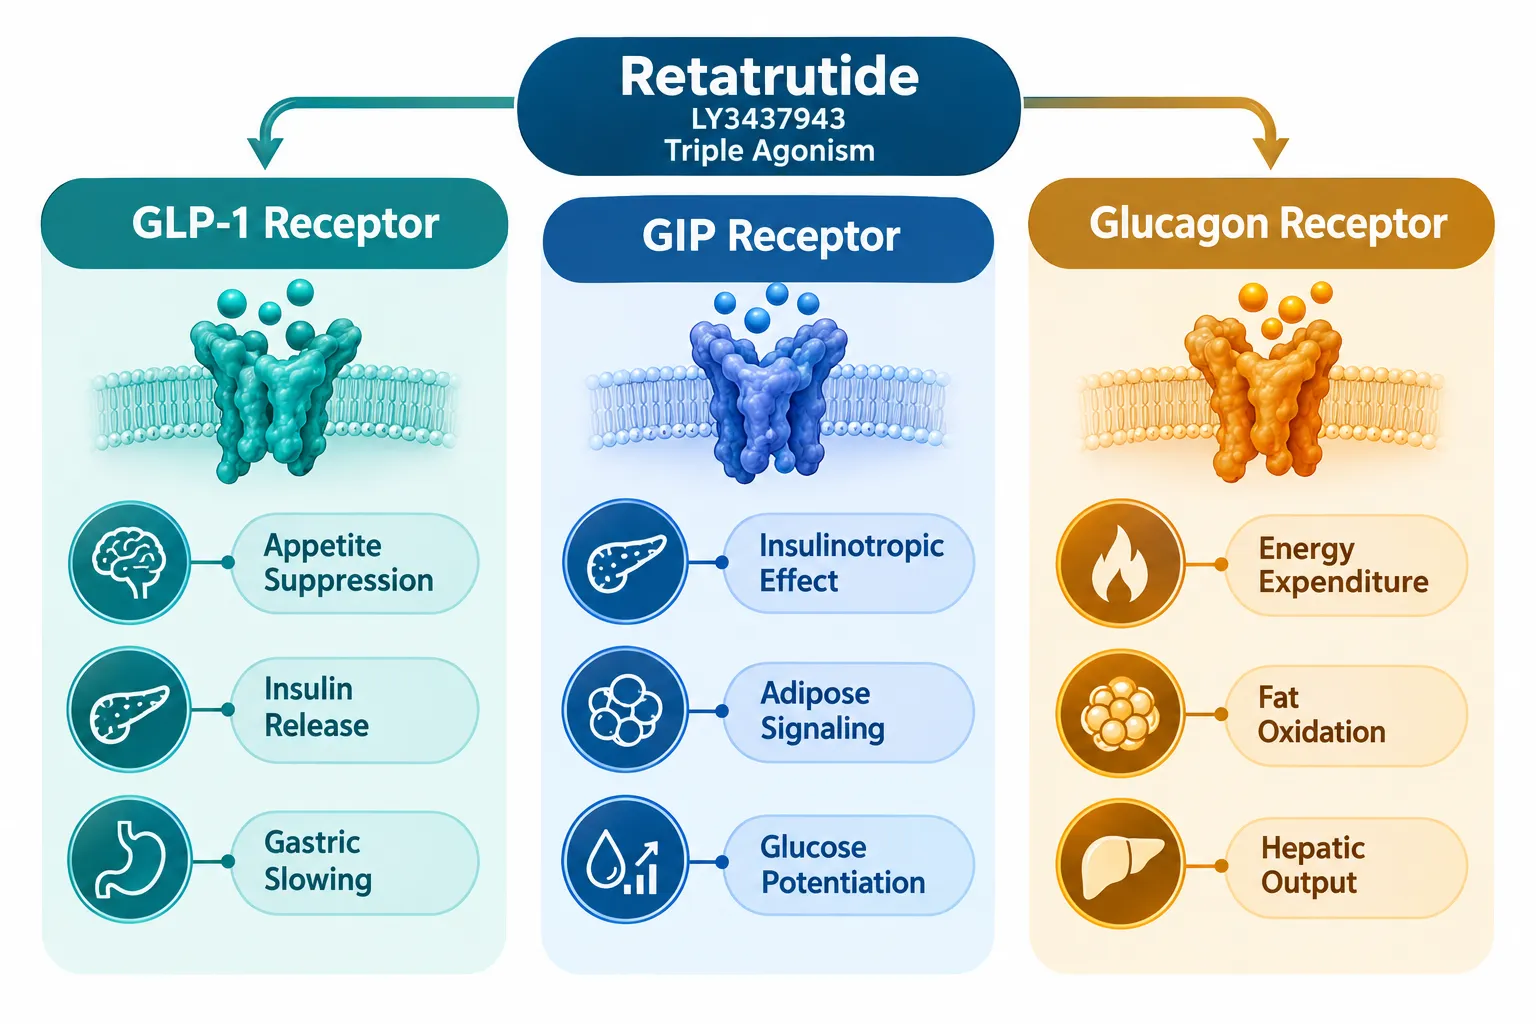
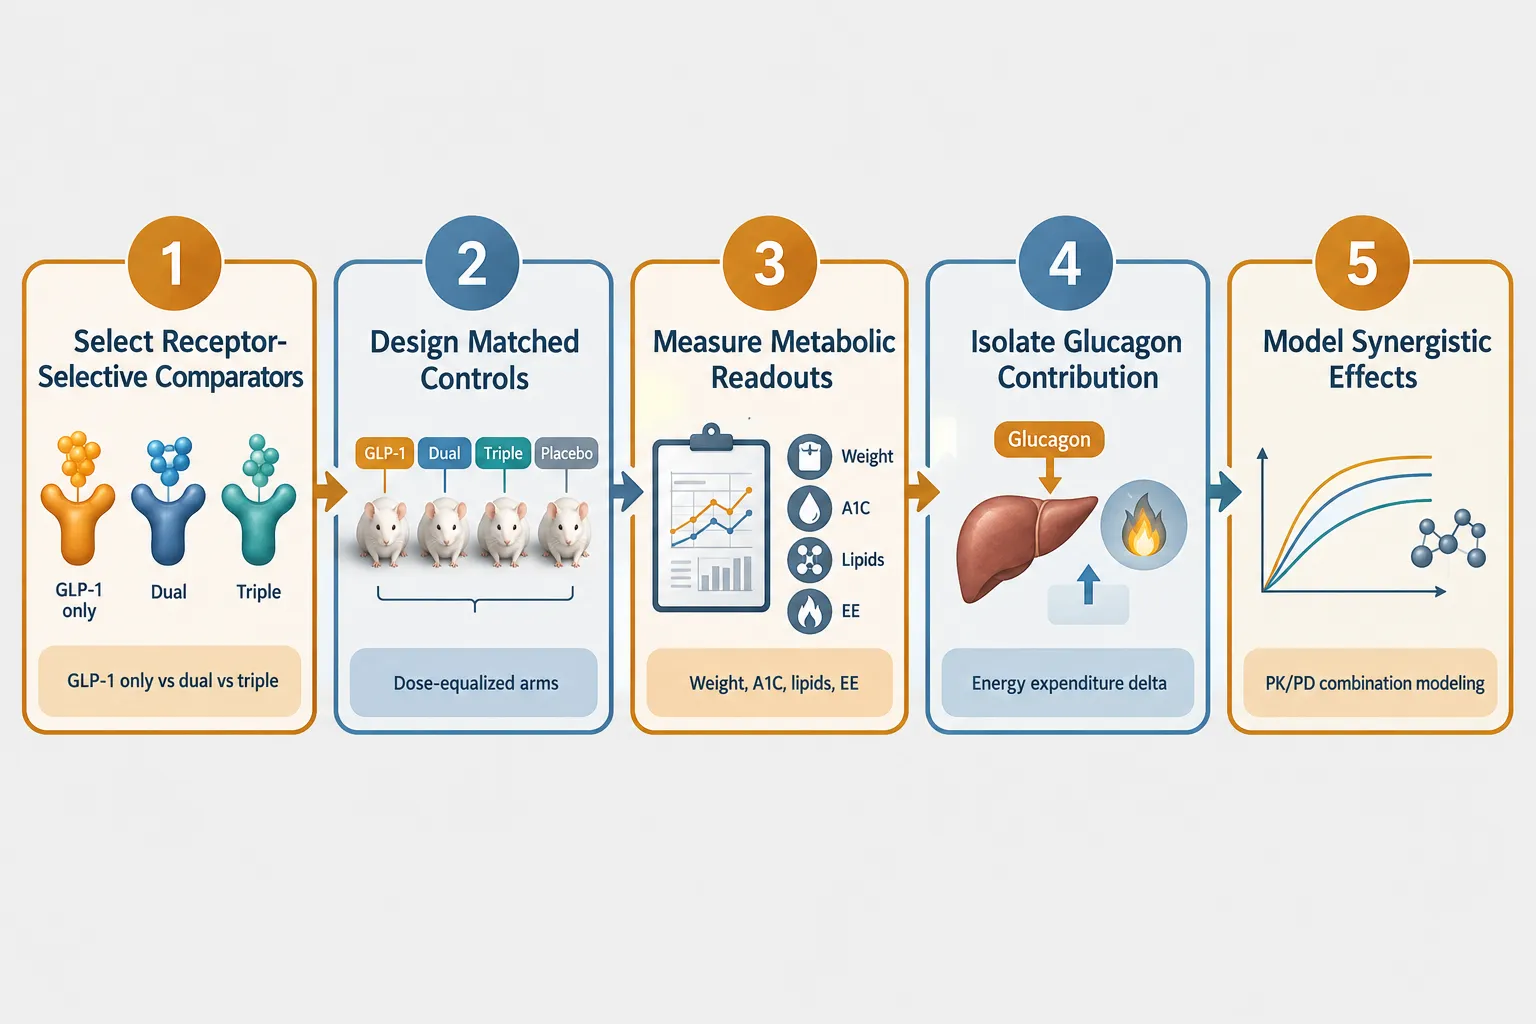
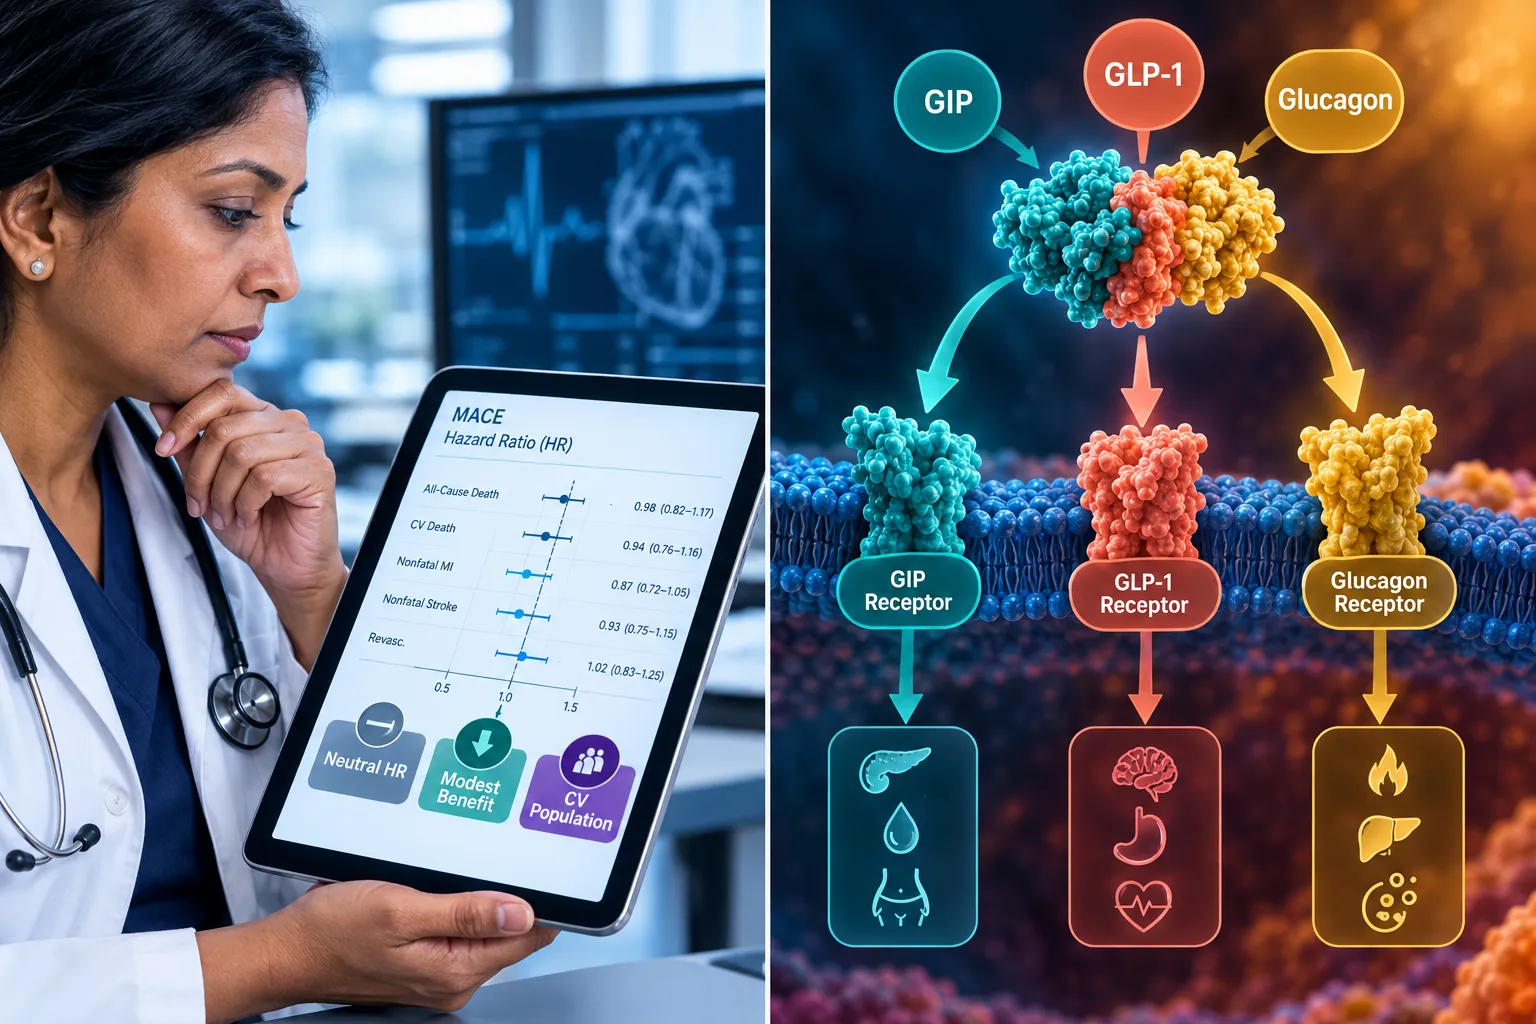
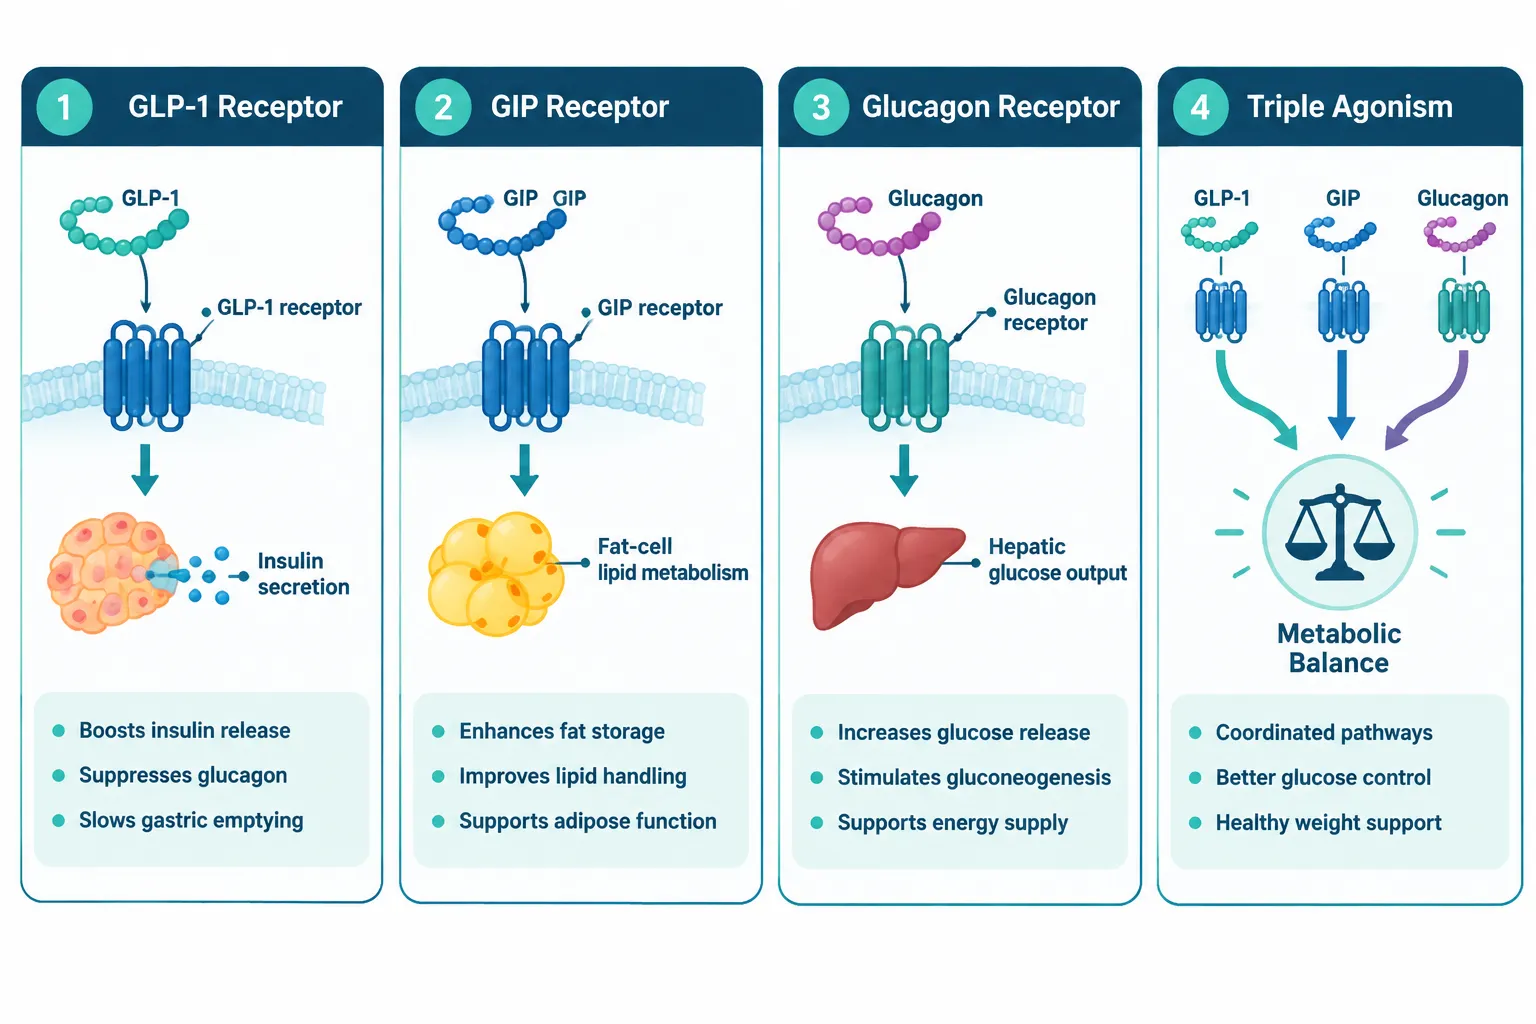
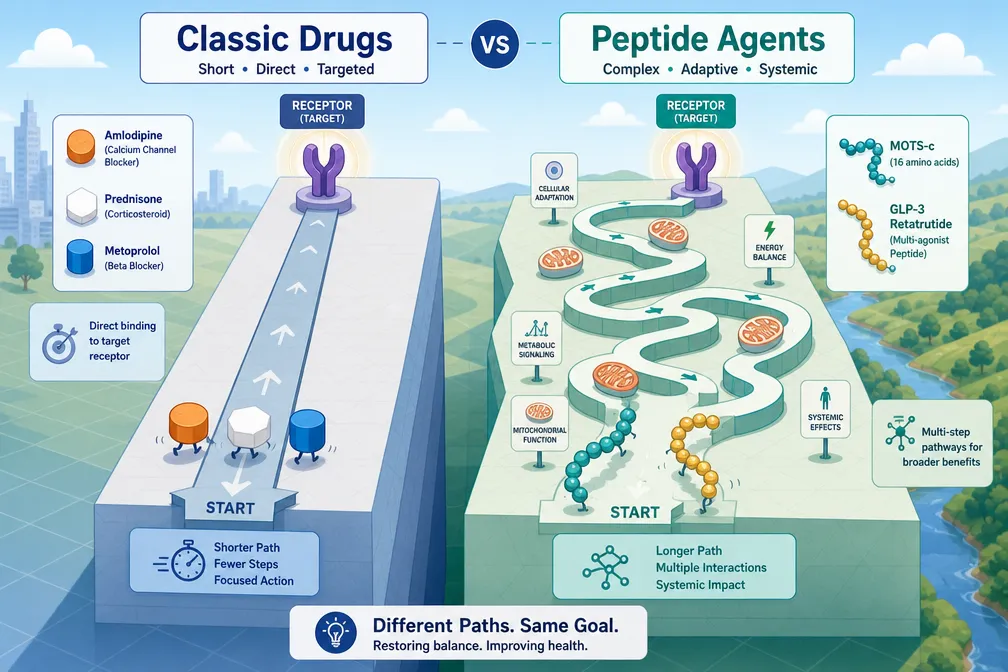
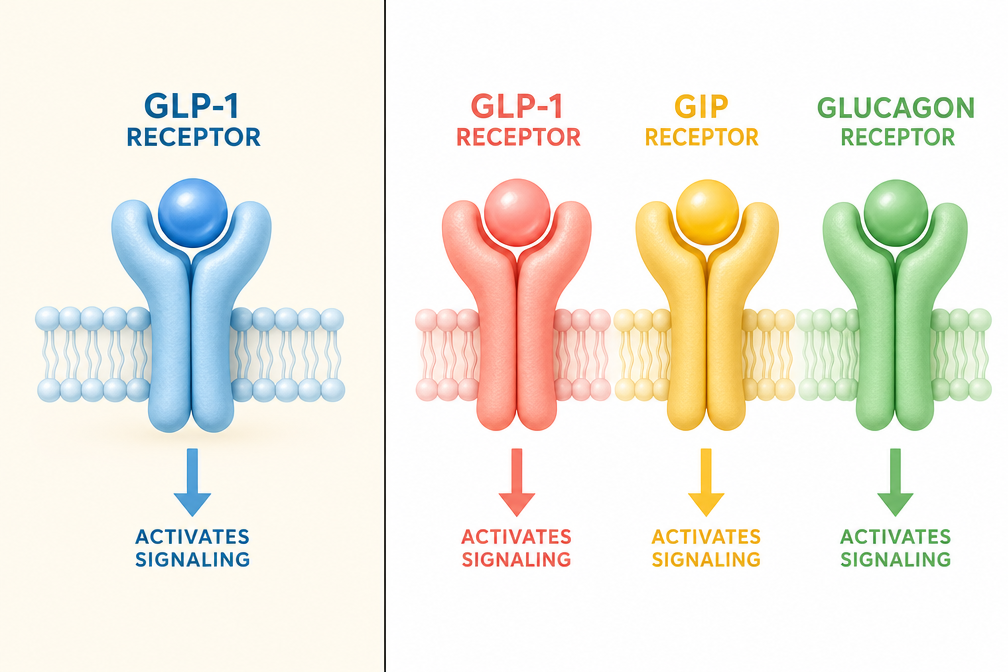
Retatrutide is a triple agonist acting at GLP-1, GIP, and glucagon receptors simultaneously. This tri-receptor mechanism creates a weight-loss signature that is both larger in magnitude and different in character from dual or single incretin agents. To understand what makes isolating that signature so difficult, and so important, it helps to know what the signature actually looks like.
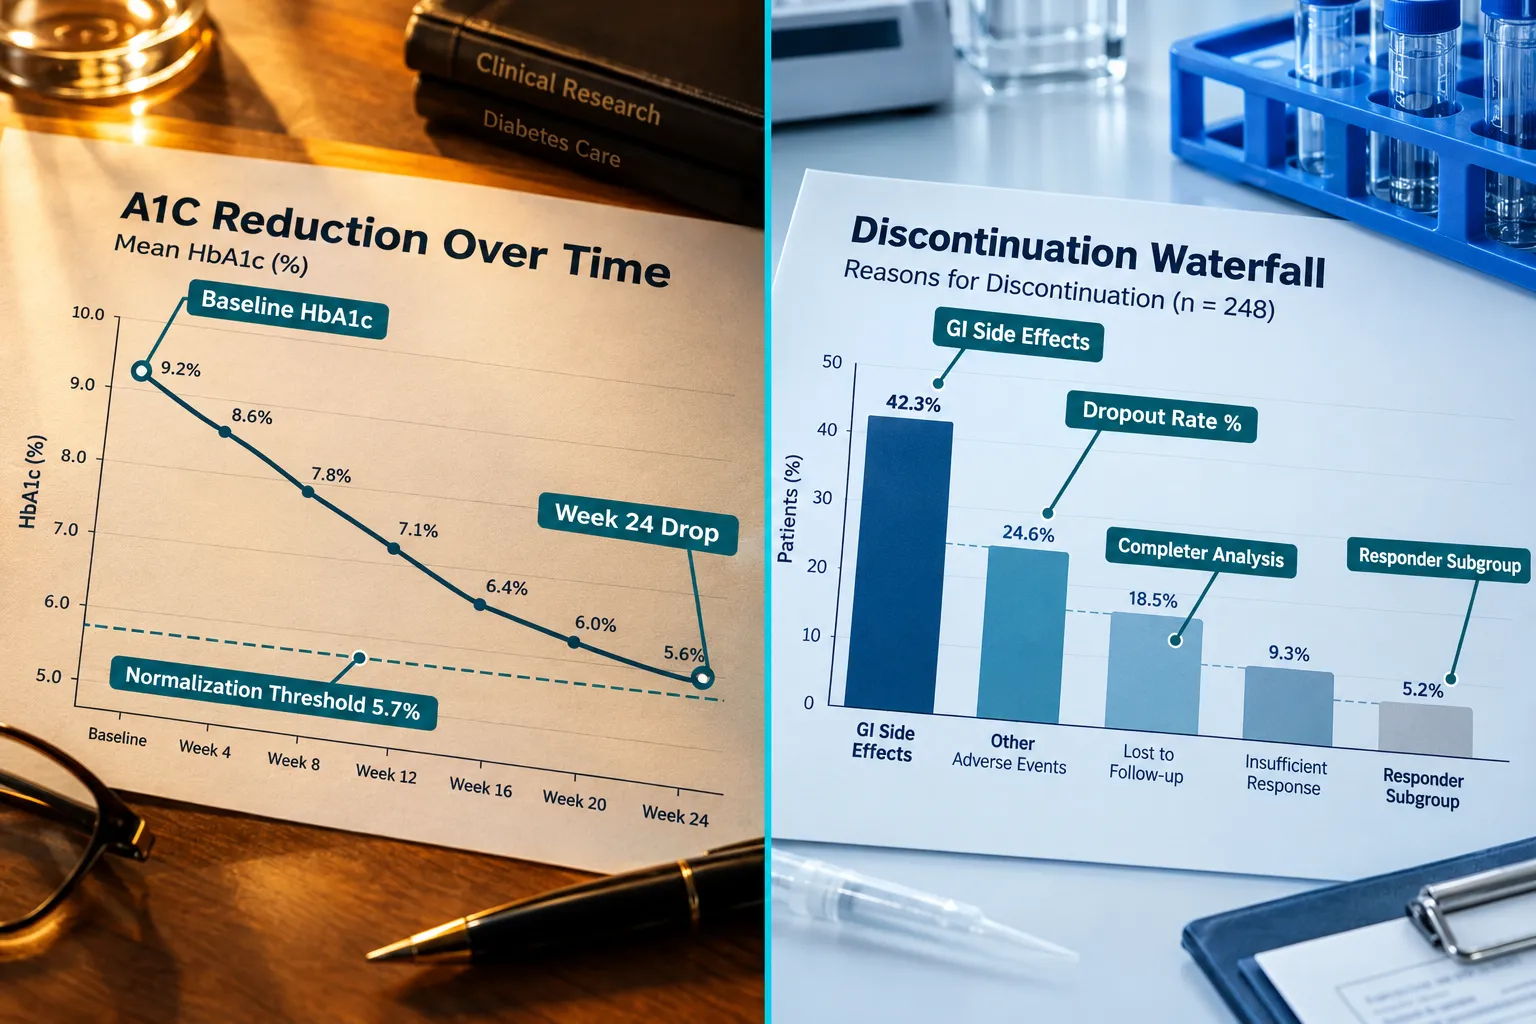
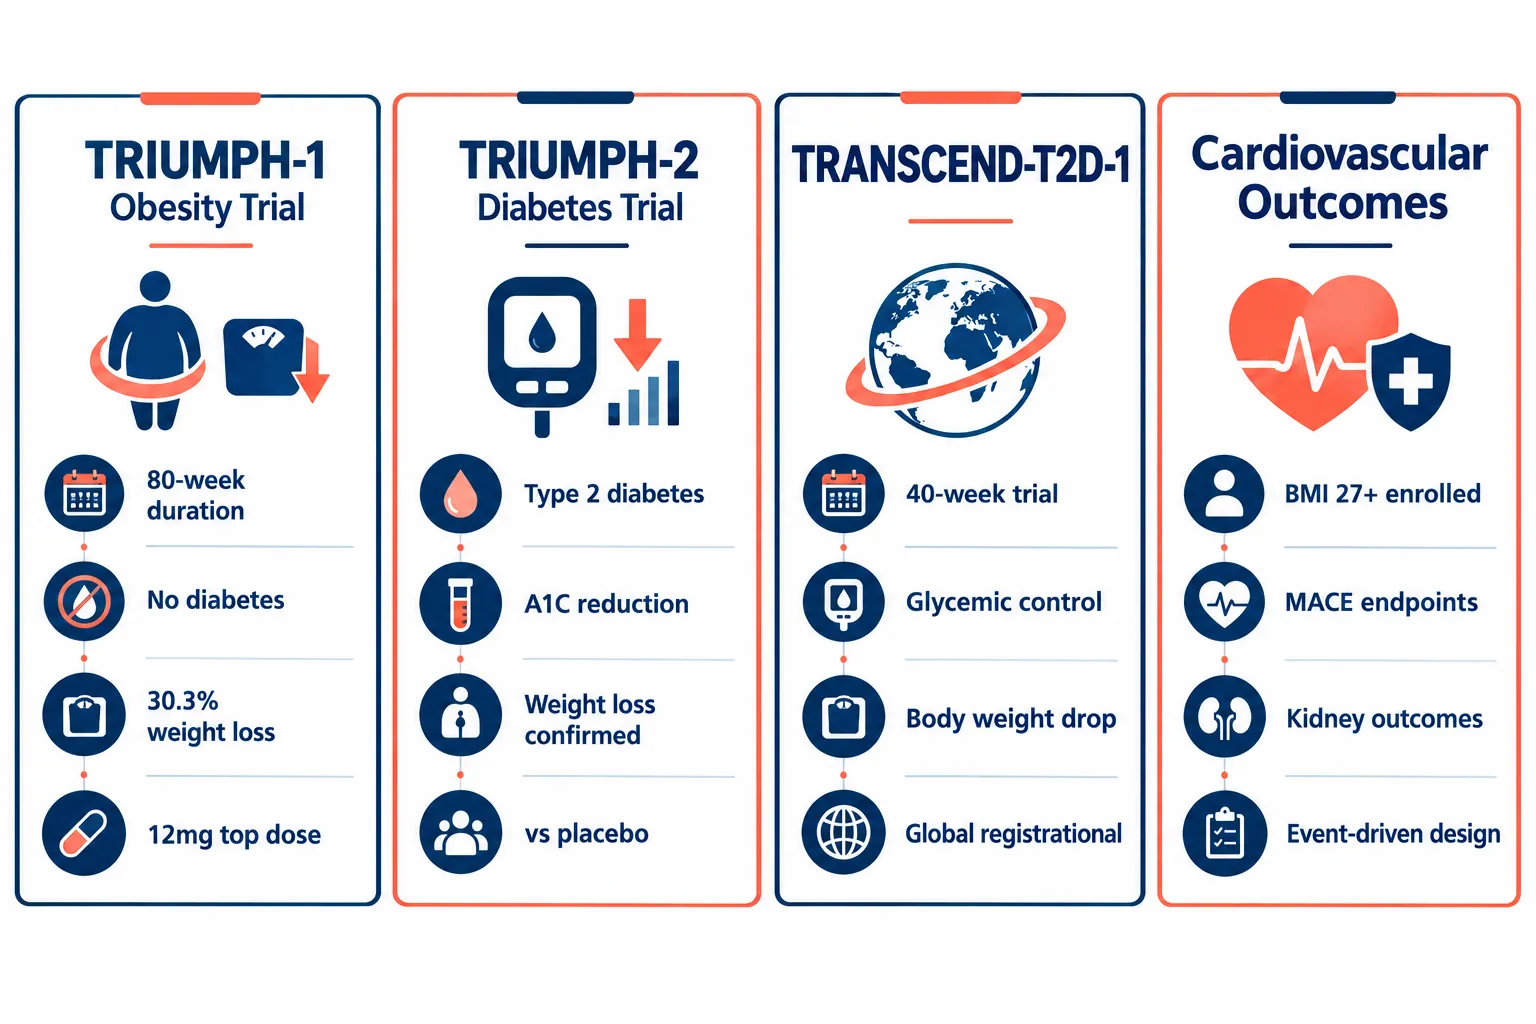
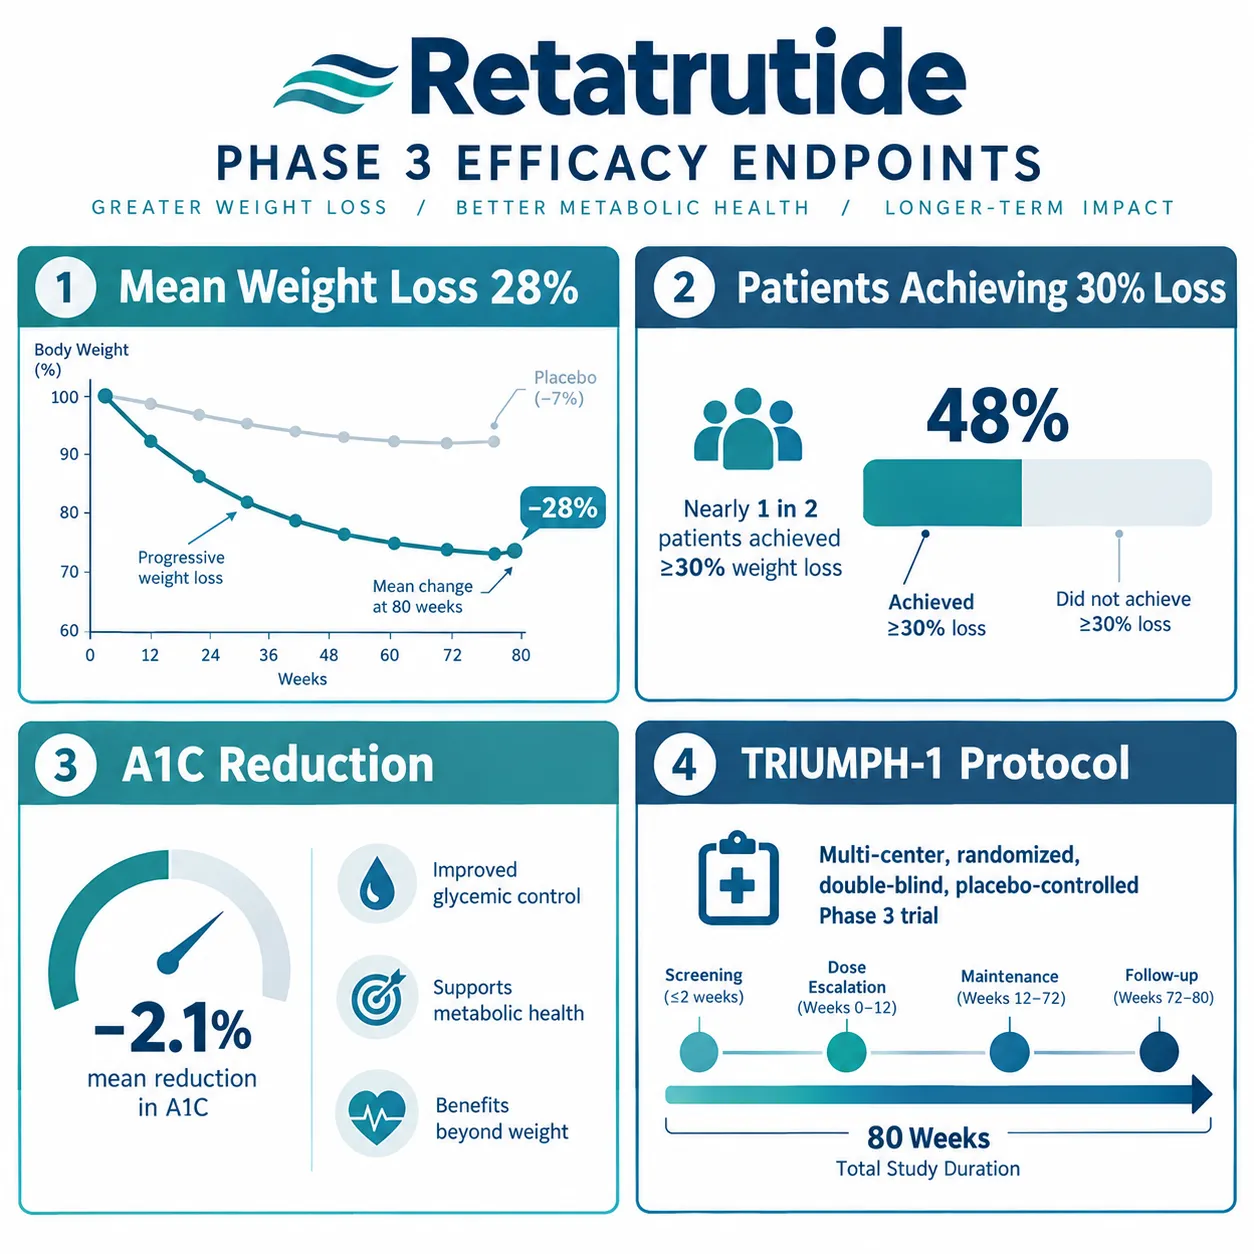
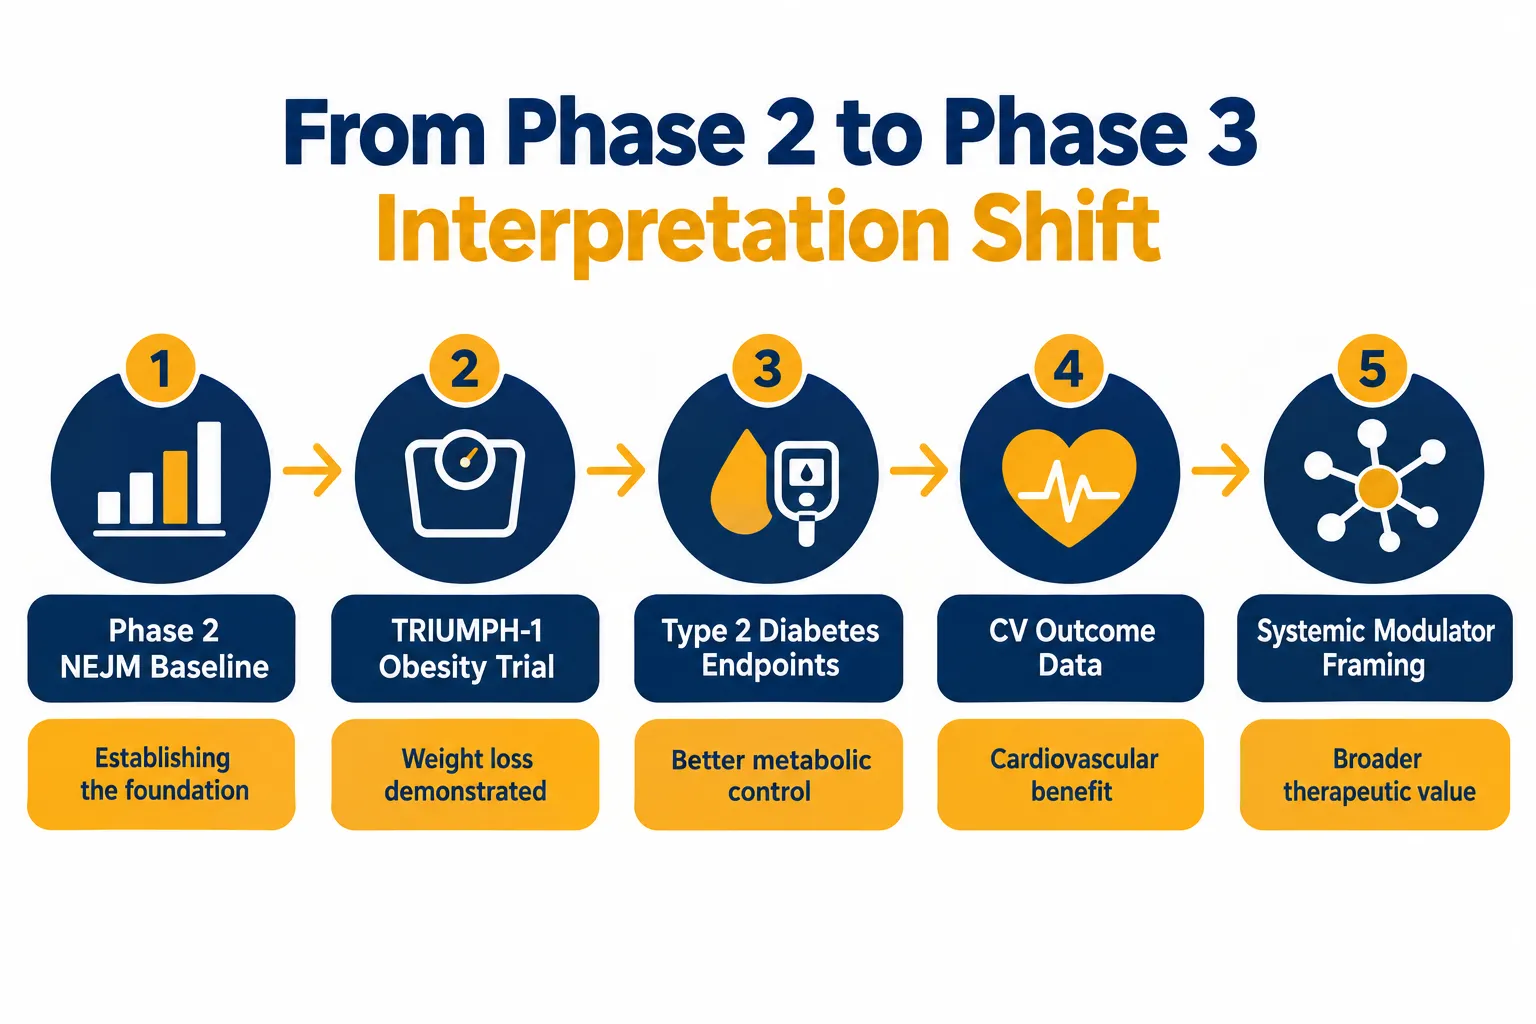
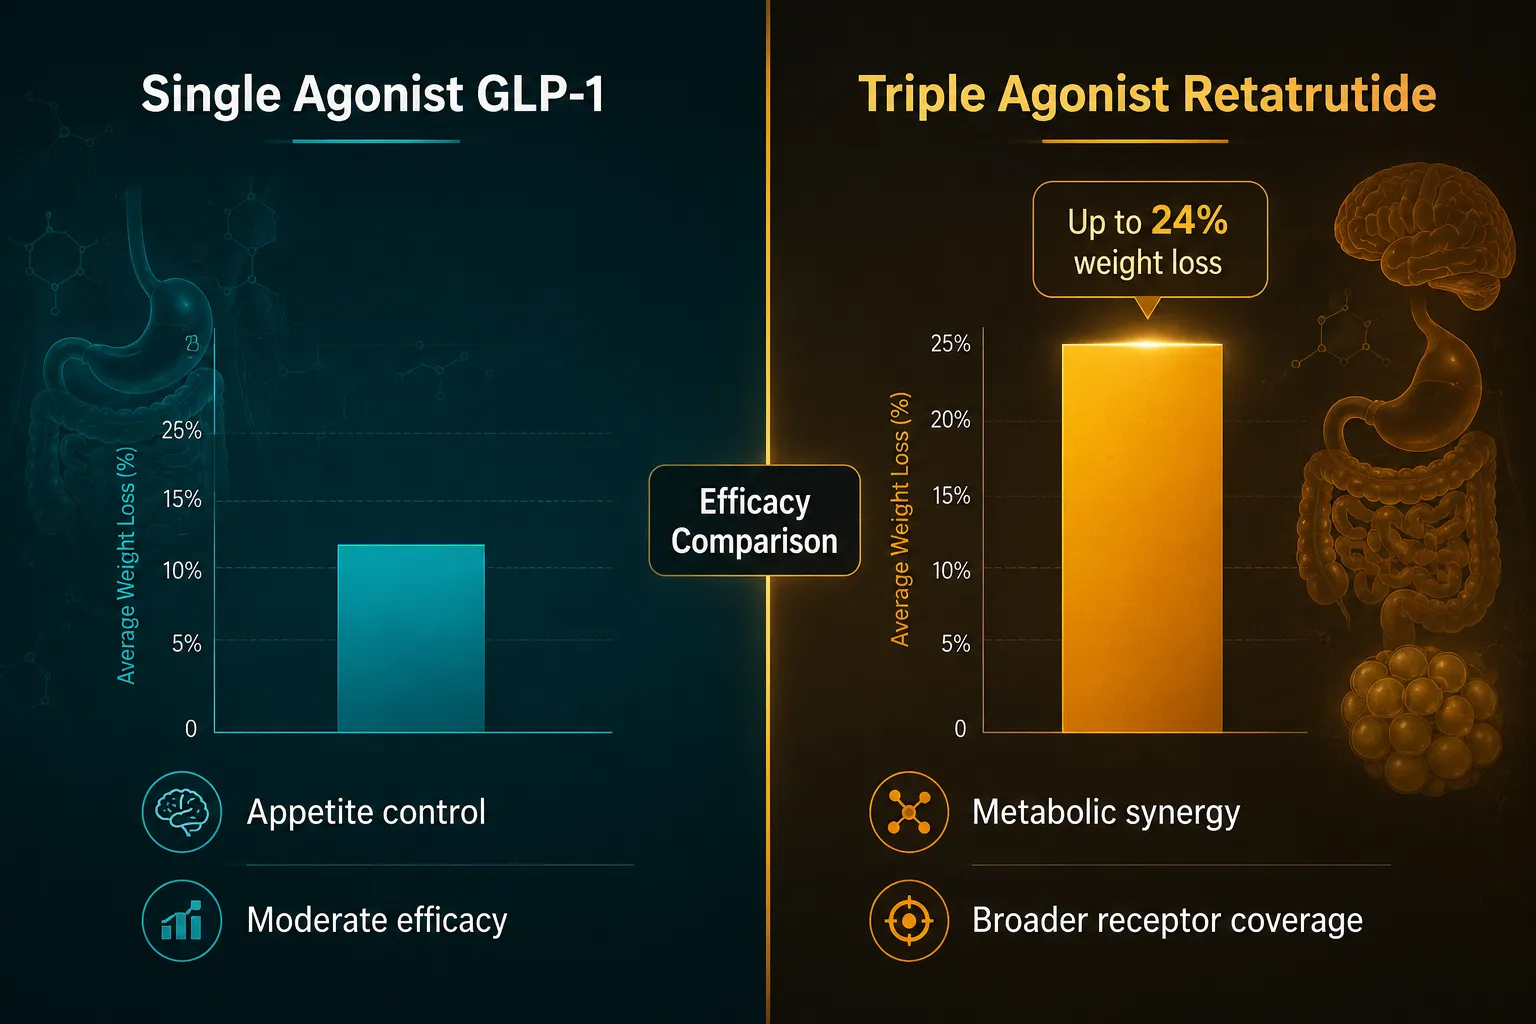
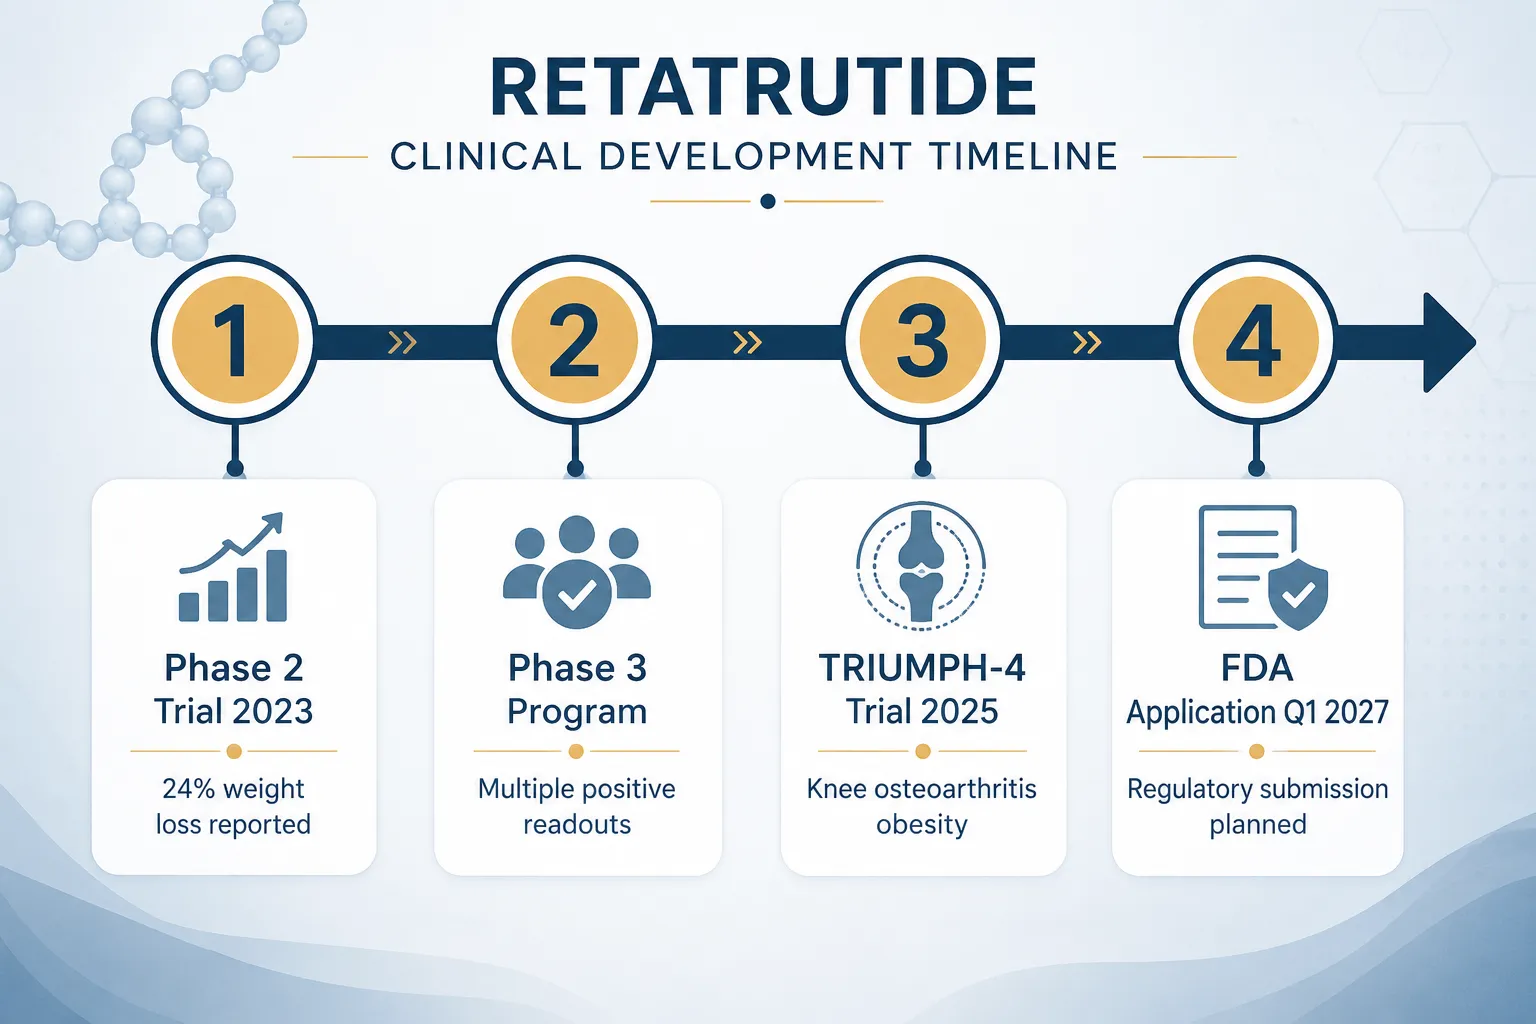
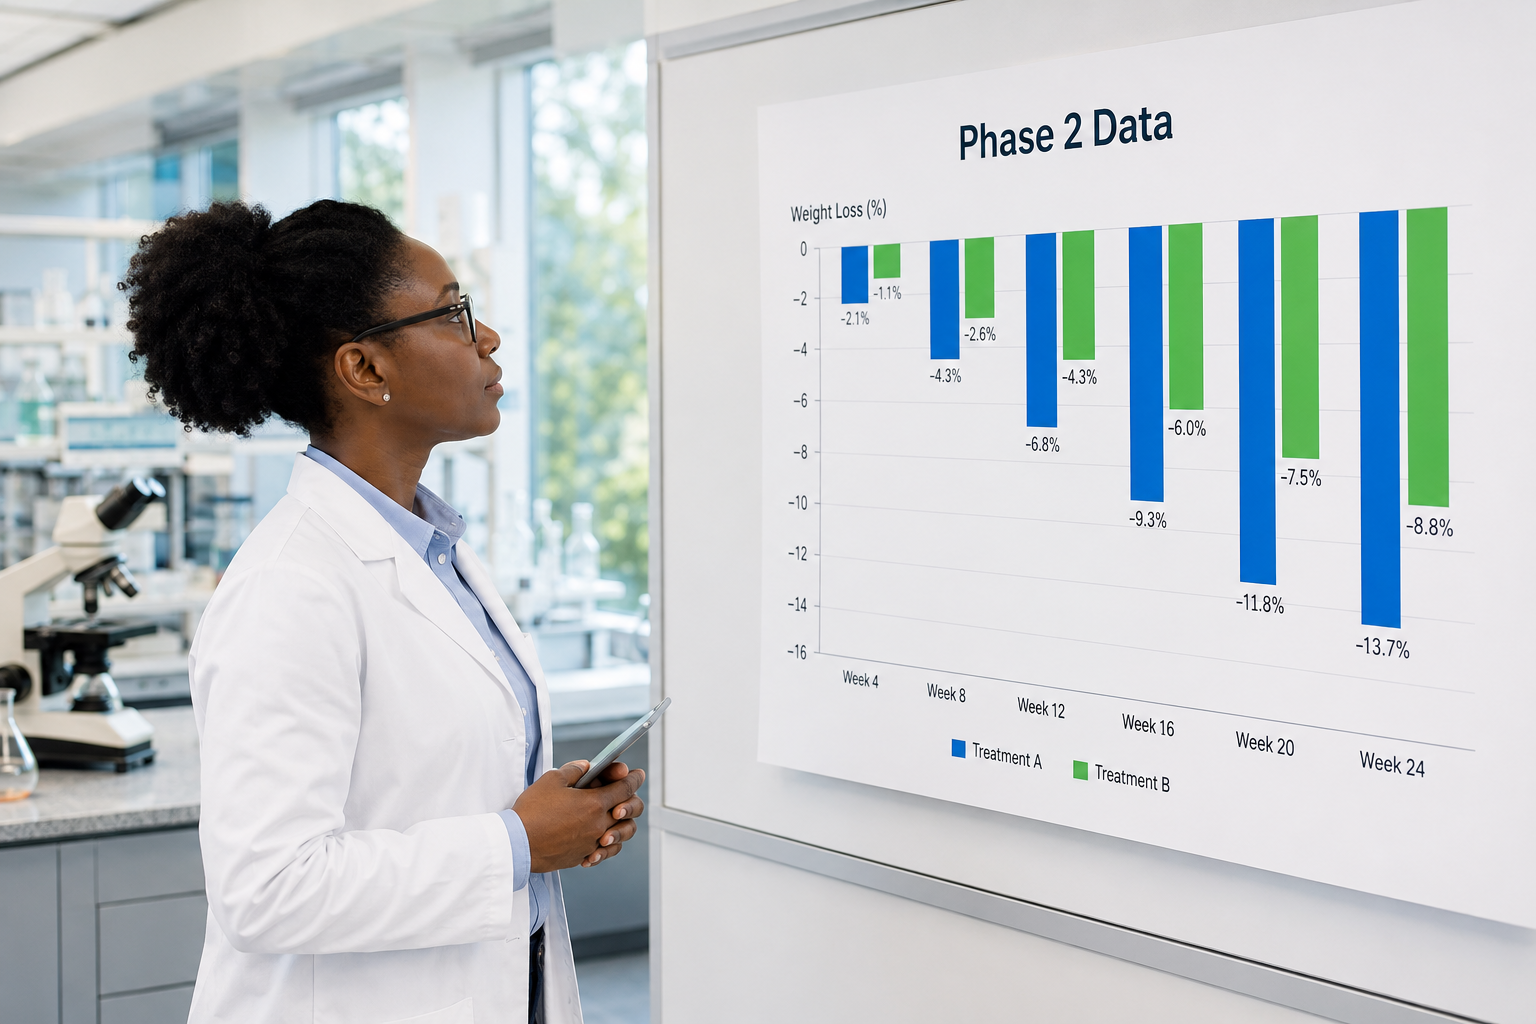
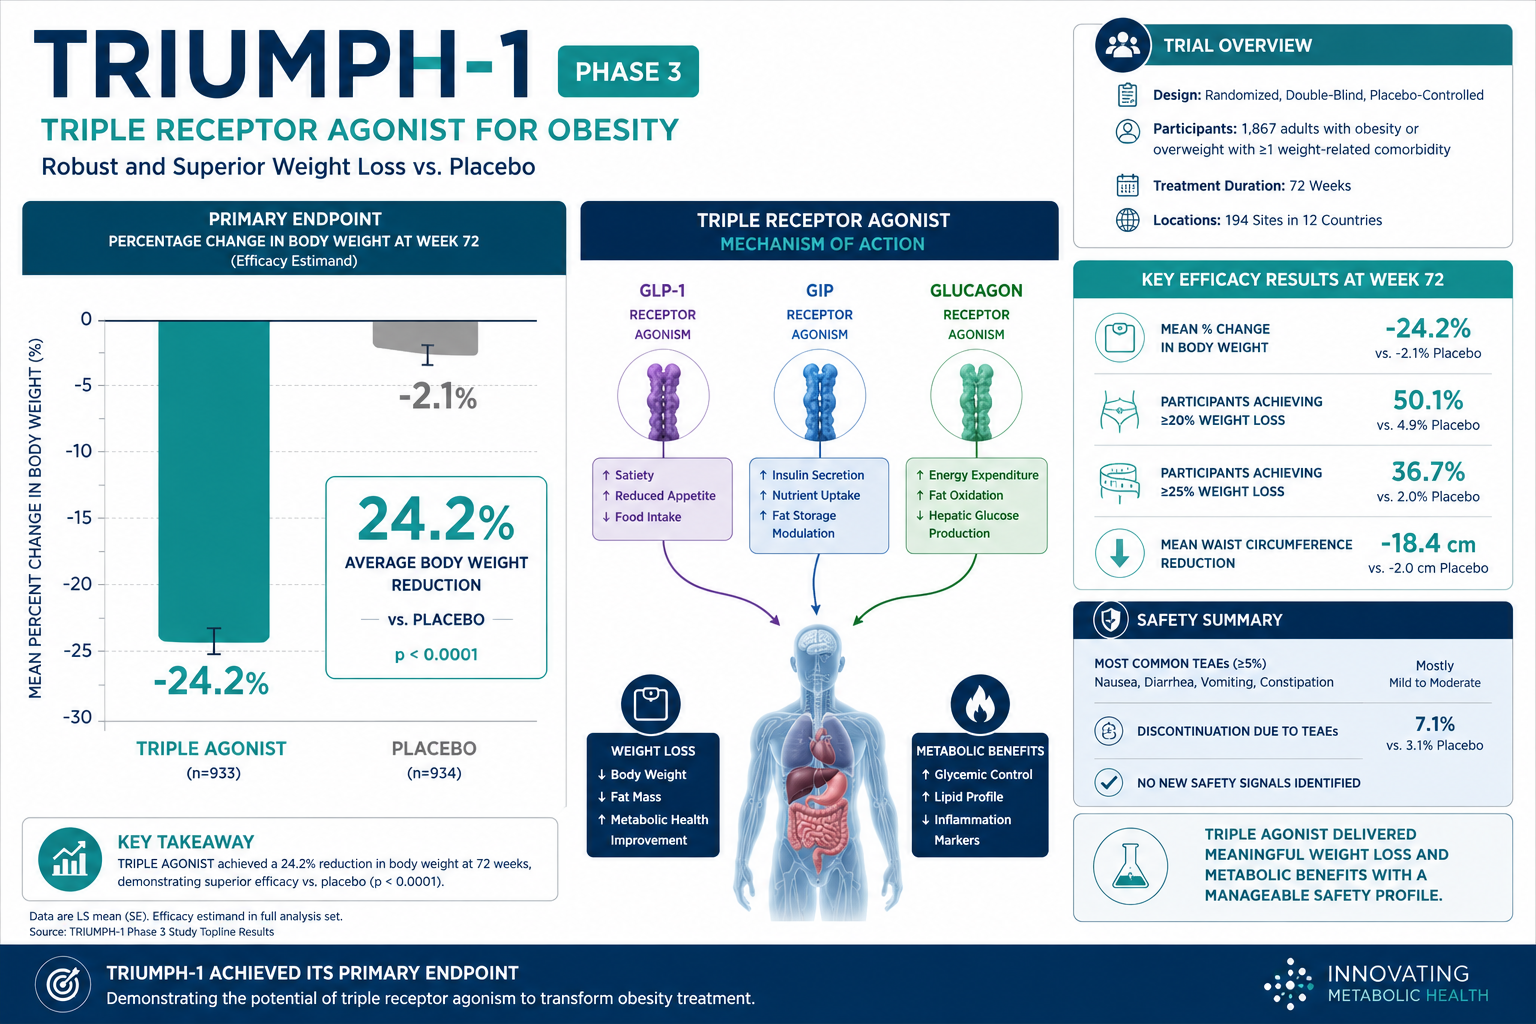
Phase 2 trial data show retatrutide producing mean weight reductions in the range of 17-24% of body weight over approximately 48 weeks, placing it among the strongest peptides for weight loss currently in clinical development. Body-composition substudies reveal that the majority of lost mass is adipose tissue, with a relatively preserved lean mass fraction, a fat-preferential signature that is pharmacologically meaningful and clinically distinguishable.
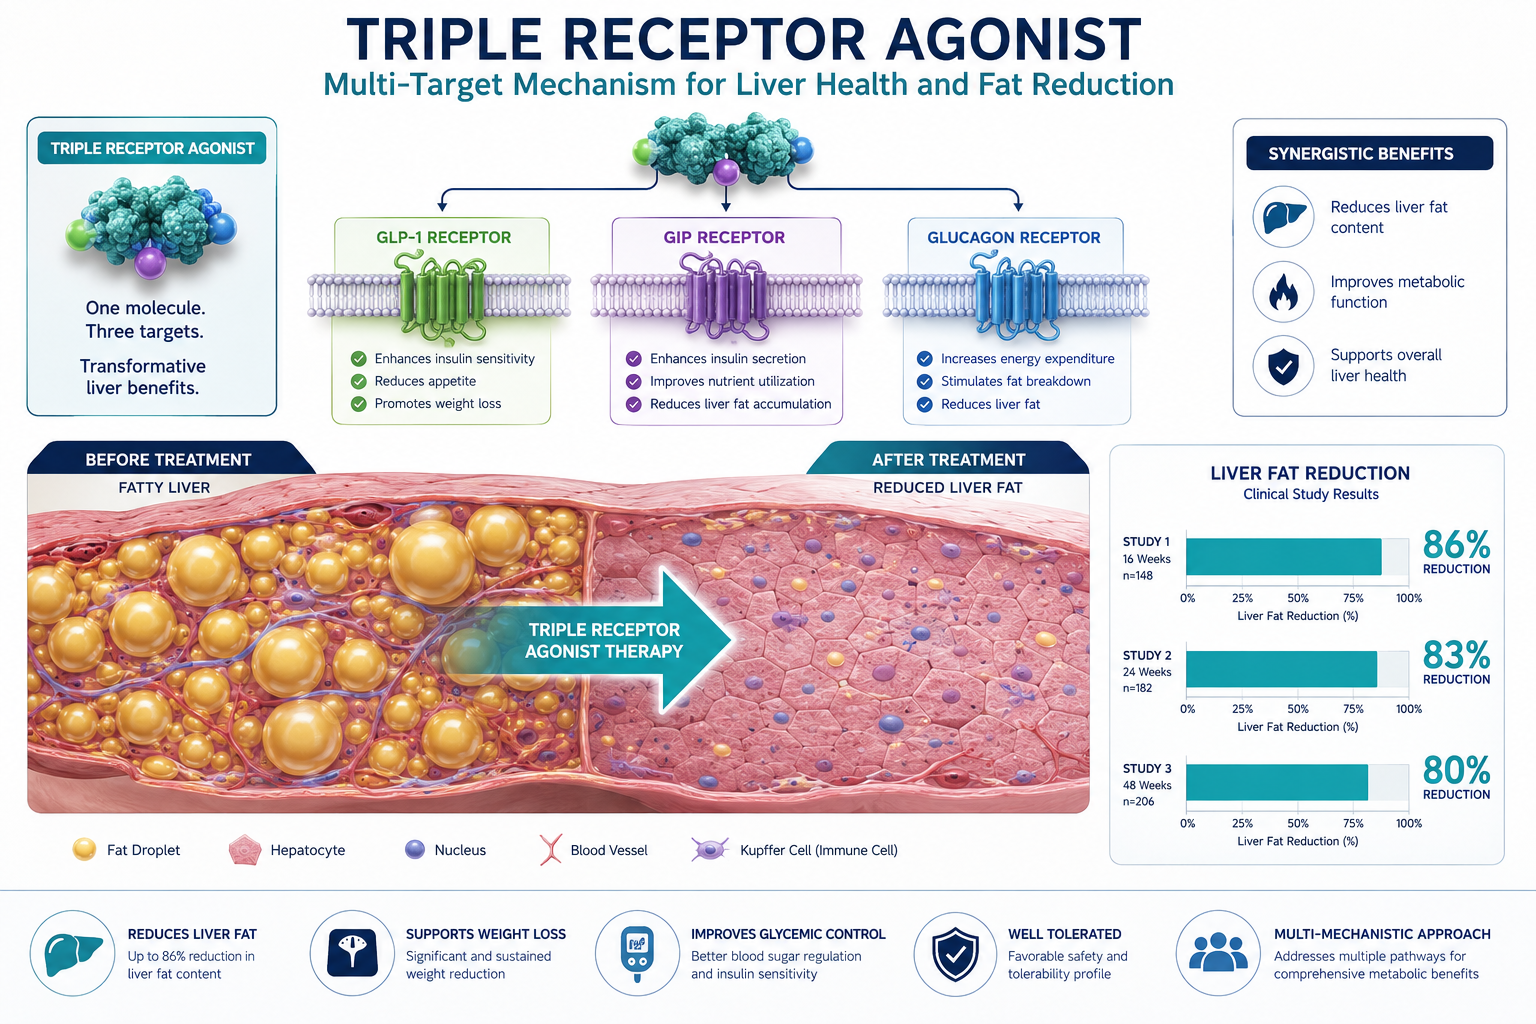
Retatrutide also shows promising results in metabolic dysfunction-associated steatotic liver disease (MASLD), reducing hepatic fat fraction alongside systemic adiposity. This multi-organ benefit makes precise attribution of metabolic changes especially important: researchers need to know whether liver improvements stem from the drug's direct action or from generalized weight loss that any intervention might have produced.
The problem is that quetiapine's pro-hyperphagic effects work in exactly the opposite direction. When a patient simultaneously experiences antipsychotic-driven appetite increases and GLP-3-driven appetite suppression, the net weight-loss signal is attenuated. The GLP-3 Reta mechanism is not negated, but its apparent magnitude shrinks. Researchers who do not account for this interaction may conclude that retatrutide underperformed when in reality the drug achieved its expected pharmacological effect against a metabolic headwind.
Three mechanisms of signal distortion:
- Hyperphagic offset, antipsychotic-driven caloric intake partially cancels appetite suppression.
- Baseline inflation, elevated pre-trial BMI and glucose shift the apparent responder rate.
- Regression-to-mean artifact, patients with quetiapine-elevated baselines show large apparent drops early if the antipsychotic dose is also adjusted during the trial.
Isolating the GLP-3 Signal: Study Design and Statistical Controls
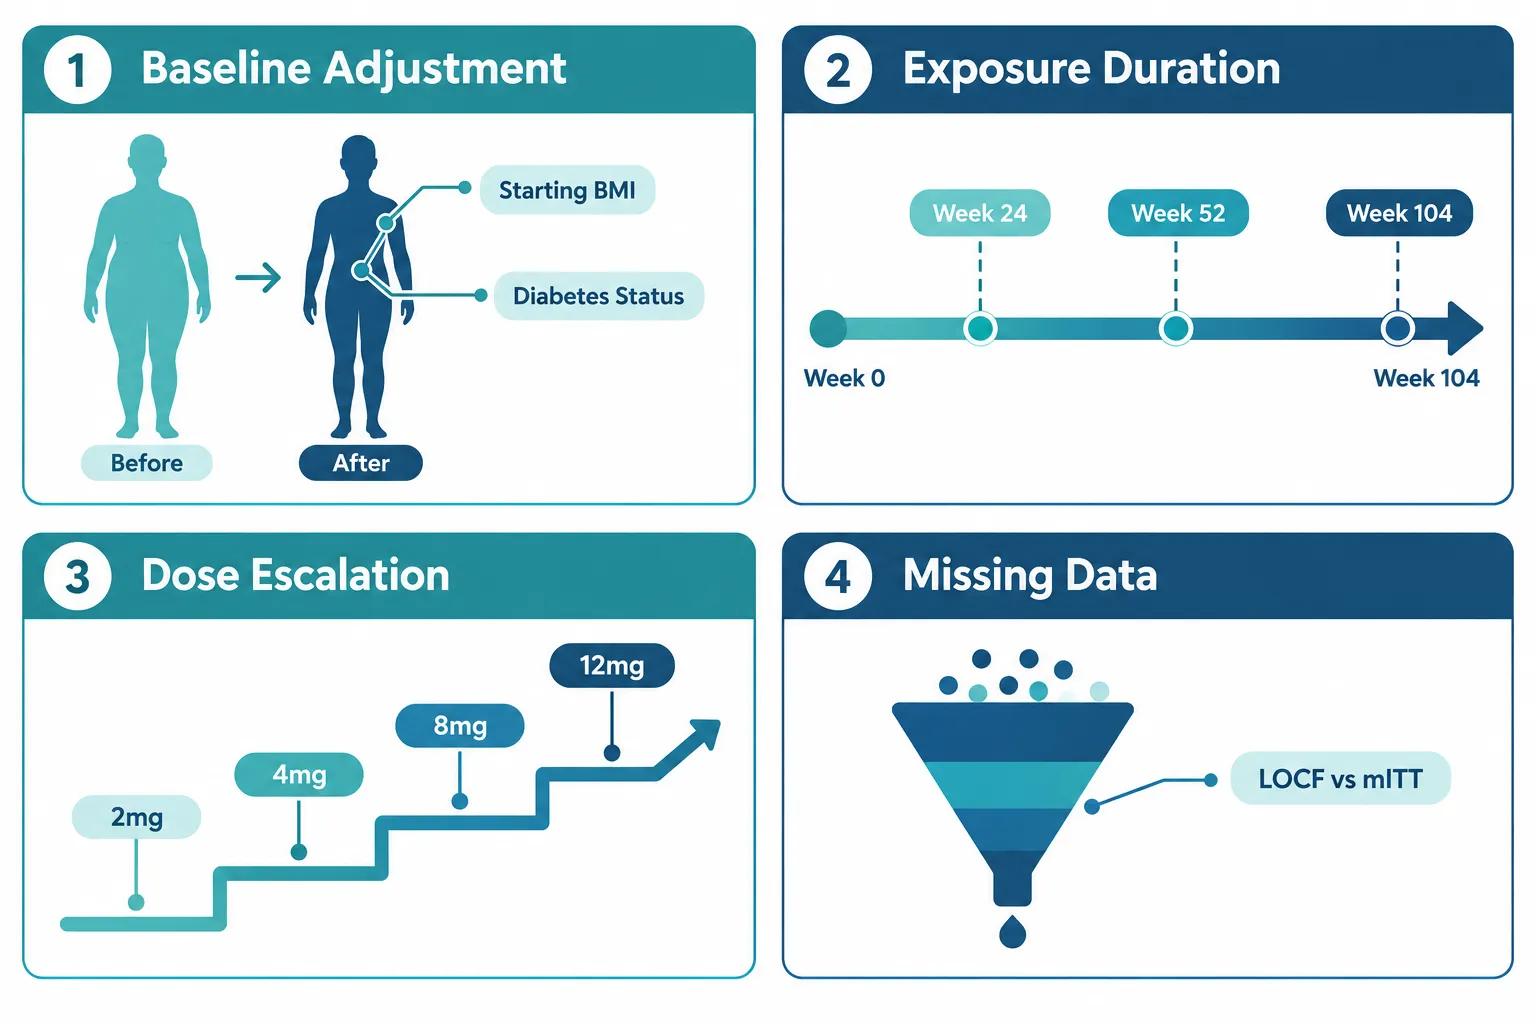
Addressing Seroquel (Quetiapine) confounding metrics in metabolic studies: isolating GLP-3 retatrutide weight loss signatures requires intervention at three levels: enrollment screening, randomization strategy, and post-hoc statistical adjustment.
Enrollment and screening protocols
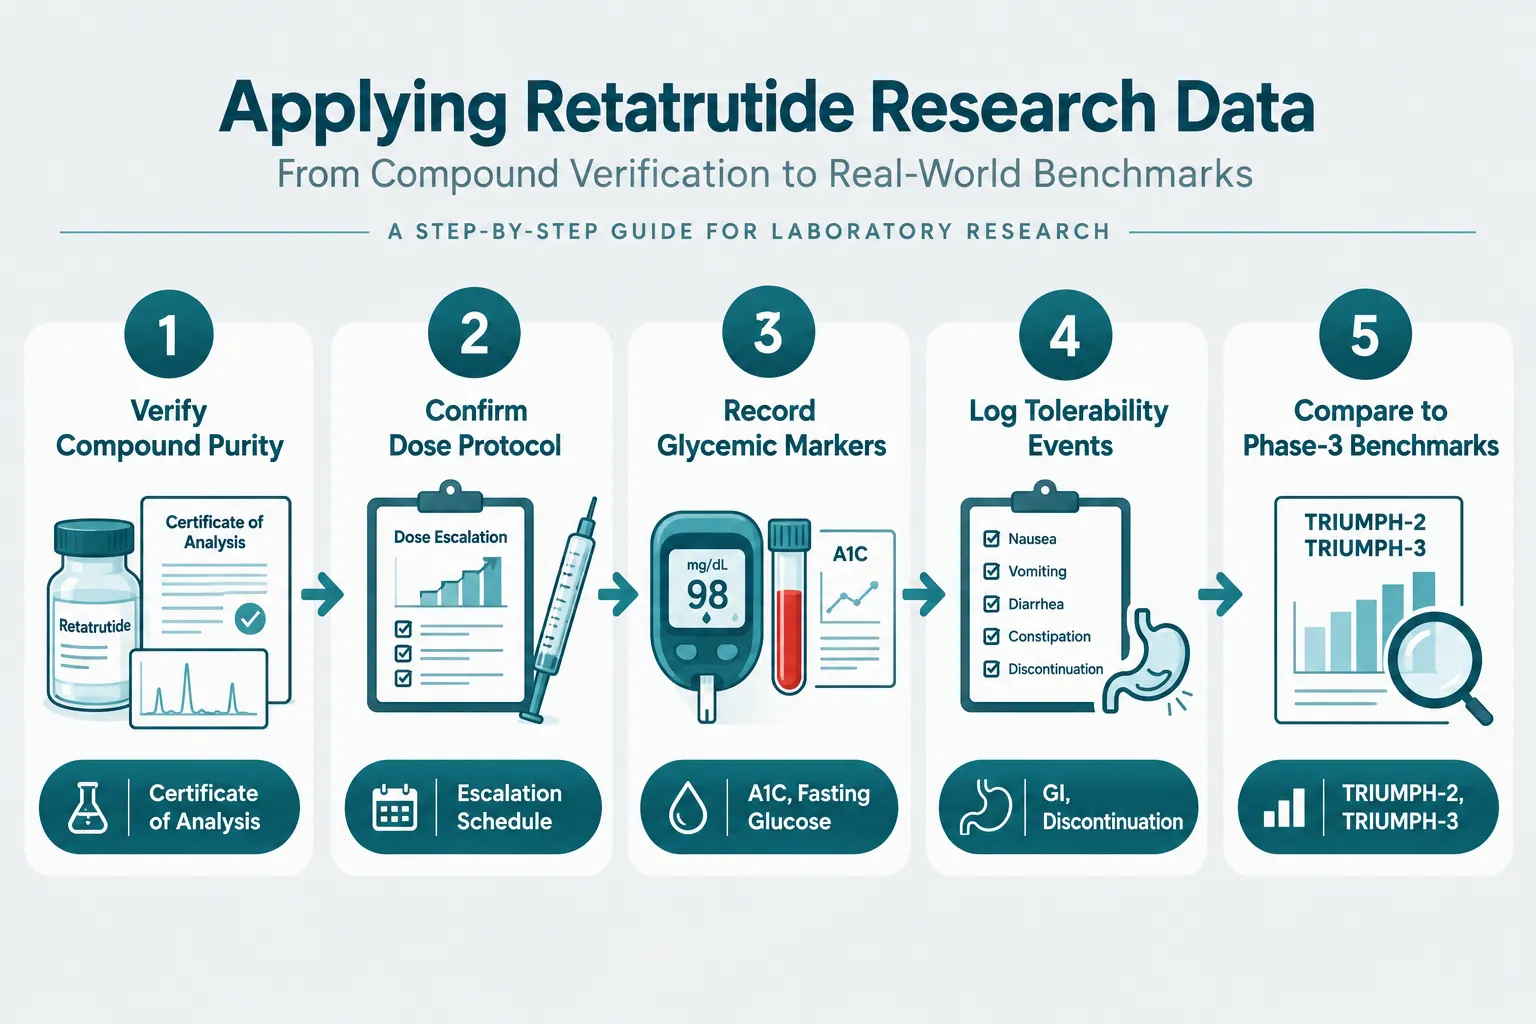
The first corrective step is comprehensive antipsychotic exposure logging at screening. This means recording not just current quetiapine use but historical dose, cumulative duration, and any dose changes in the 90 days before enrollment. Researchers sourcing Reta peptide for preclinical work should apply the same principle: animal models with prior antipsychotic exposure require separate analysis tracks.
Stratified randomization
Participants should be stratified by quetiapine exposure status (none, low-dose, high-dose, discontinued) before randomization. This prevents accidental clustering of antipsychotic users in one arm and ensures that any residual confounding is balanced across groups.
Covariate adjustment models
Post-hoc, quetiapine dose and duration should enter the regression model as continuous covariates alongside standard metabolic variables. Mixed-effects models that account for time-varying quetiapine dose changes are especially valuable in longer trials where psychiatric medication management may shift.
Subgroup-specific benchmarks
Quantitative expectations for retatrutide weight loss differ meaningfully between antipsychotic-naive participants and those carrying metabolic burden from quetiapine. Establishing drug-class-specific response benchmarks, rather than applying a single trial-wide threshold, improves sensitivity for detecting true responders in each subgroup.
Researchers and clinicians sourcing Reta 20mg or GLP-3 Reta 30mg formulations for investigational use should document all concomitant medications with metabolic implications. For broader context on available formulations, the Glp3 Reta Cag 10mg option may also be relevant depending on dosing protocol.
- Screen all participants for current and recent antipsychotic use
- Record quetiapine dose, duration, and formulation (immediate vs. extended-release)
- Stratify randomization by antipsychotic exposure category
- Include quetiapine dose as a time-varying covariate in primary analysis
- Pre-specify subgroup analyses for quetiapine-exposed vs. naive participants
- Apply drug-class-specific response benchmarks when interpreting efficacy
Conclusion
The intersection of Seroquel (Quetiapine) confounding metrics in metabolic studies: isolating GLP-3 retatrutide weight loss signatures represents one of the most practically important, and most overlooked, design challenges in modern obesity pharmacology. Quetiapine's well-documented capacity to drive weight gain, dysregulate glucose metabolism, and blunt satiety signaling creates a systematic bias that can shrink or distort the apparent efficacy of one of the most potent incretin agents in development.
Actionable next steps for researchers and clinicians:
- Implement mandatory antipsychotic exposure screening in all retatrutide and incretin-class trial protocols starting in 2026.
- Adopt stratified randomization as a standard rather than optional design element.
- Pre-register subgroup analyses for antipsychotic-exposed participants so results are not dismissed as post-hoc.
- Collaborate with psychiatric co-investigators to capture real-world quetiapine dose fluctuations that occur during long trials.
- Apply drug-specific metabolic benchmarks when counseling patients currently on quetiapine who are beginning GLP-3 therapy, so that attenuated early response is correctly interpreted rather than misread as treatment failure.
The weight-loss signature that retatrutide produces is pharmacologically robust. Protecting its visibility in data, by rigorously controlling for antipsychotic-induced metabolic dysfunction, is the research community's responsibility.