Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: cjc-1295

CJC-1295 With DAC vs Without DAC: How Sampling Windows Change GH-Pulse and IGF-1 Research

September 30, 2026/0 Comments/in Uncategorized/by

Cover Image

Choosing the wrong blood draw schedule can make a potent growth hormone secretagogue look completely inert, or turn a modest response into a misleading peak. That single design flaw has quietly distorted more than a few preclinical datasets involving CJC-1295 With DAC vs Without DAC: How Sampling Windows Change GH-Pulse and IGF-1 Research, and understanding why requires looking past basic mechanism summaries into the practical architecture of experimental design.

Key Takeaways

  • CJC-1295 with DAC produces a sustained, "flattened" GH profile; without DAC, GH pulses are sharp and brief, each demands a different sampling strategy.
  • Using a long sampling window for the no-DAC form will miss most GH spikes; using short windows for the DAC form will misread baseline elevation as a blunted response.
  • IGF-1 is an integrated marker of multi-day GH exposure, making it more reliable for DAC studies and less informative for short-acting analog studies.
  • Washout planning is critical: DAC's extended half-life requires days-long clearance periods, while no-DAC analogs clear within hours.
  • No randomized head-to-head trial with harmonized sampling windows has yet been published, leaving interpretation gaps that experimental design choices can either widen or close.

The Core Pharmacokinetic Difference That Drives Everything

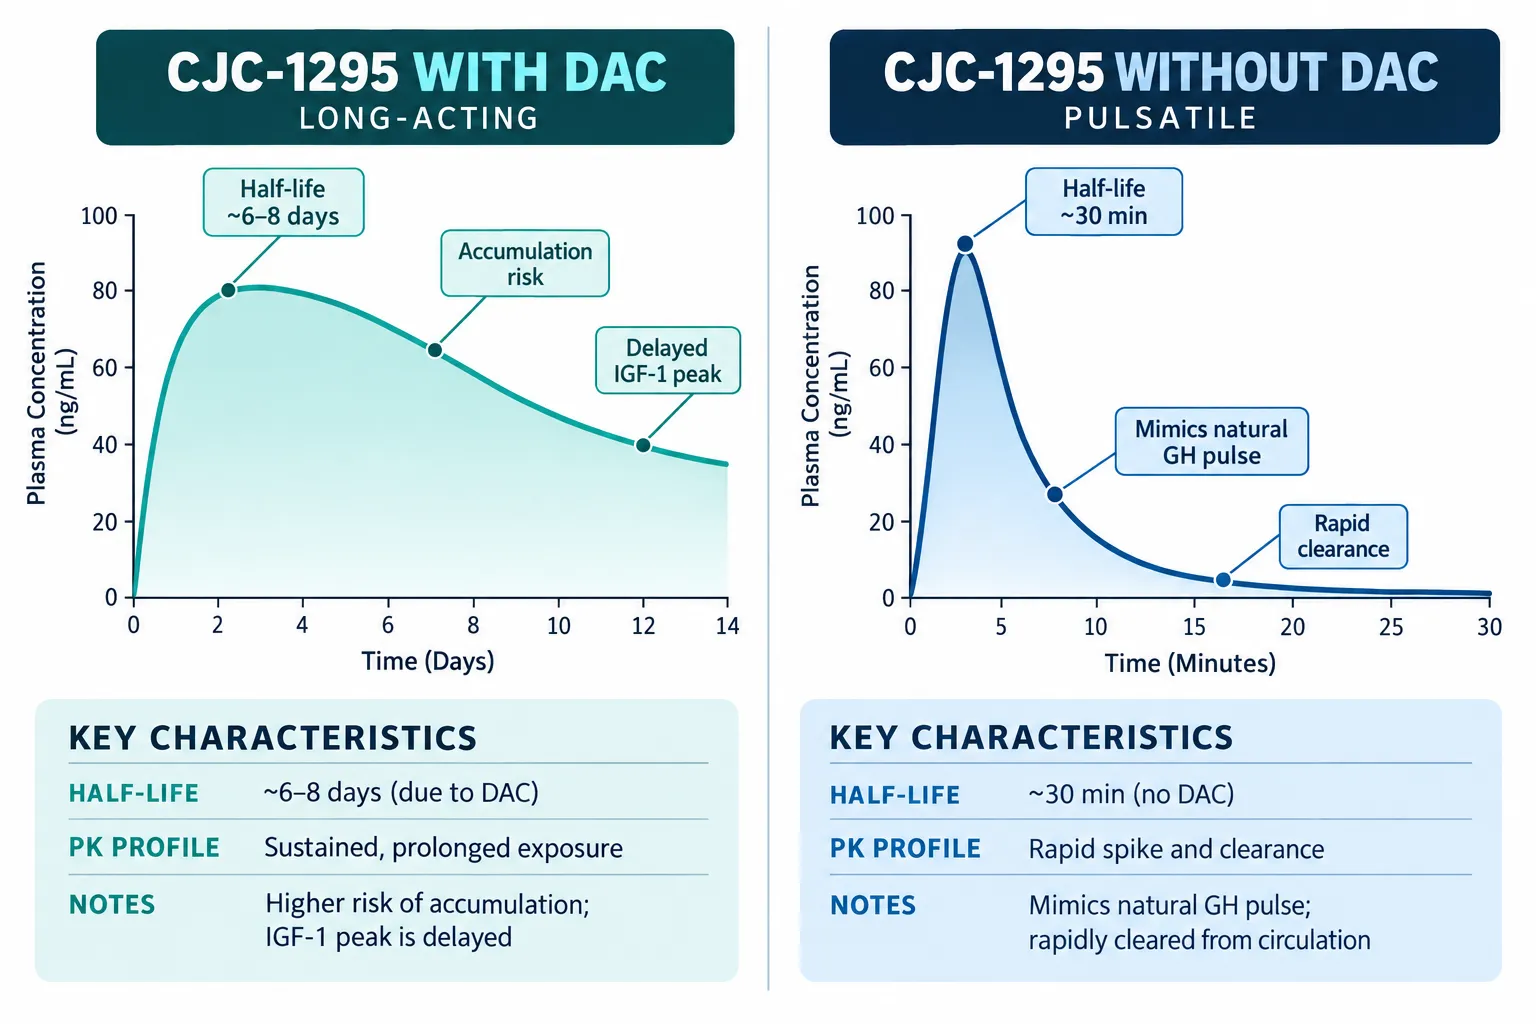
GH pulse profile comparison: DAC vs no-DAC waveforms

Before any sampling window discussion makes sense, the pharmacokinetic gap between the two forms must be clear. For a detailed breakdown of the underlying mechanisms, the CJC-1295 with and without DAC mechanism and pharmacokinetic comparison resource provides an excellent foundation.

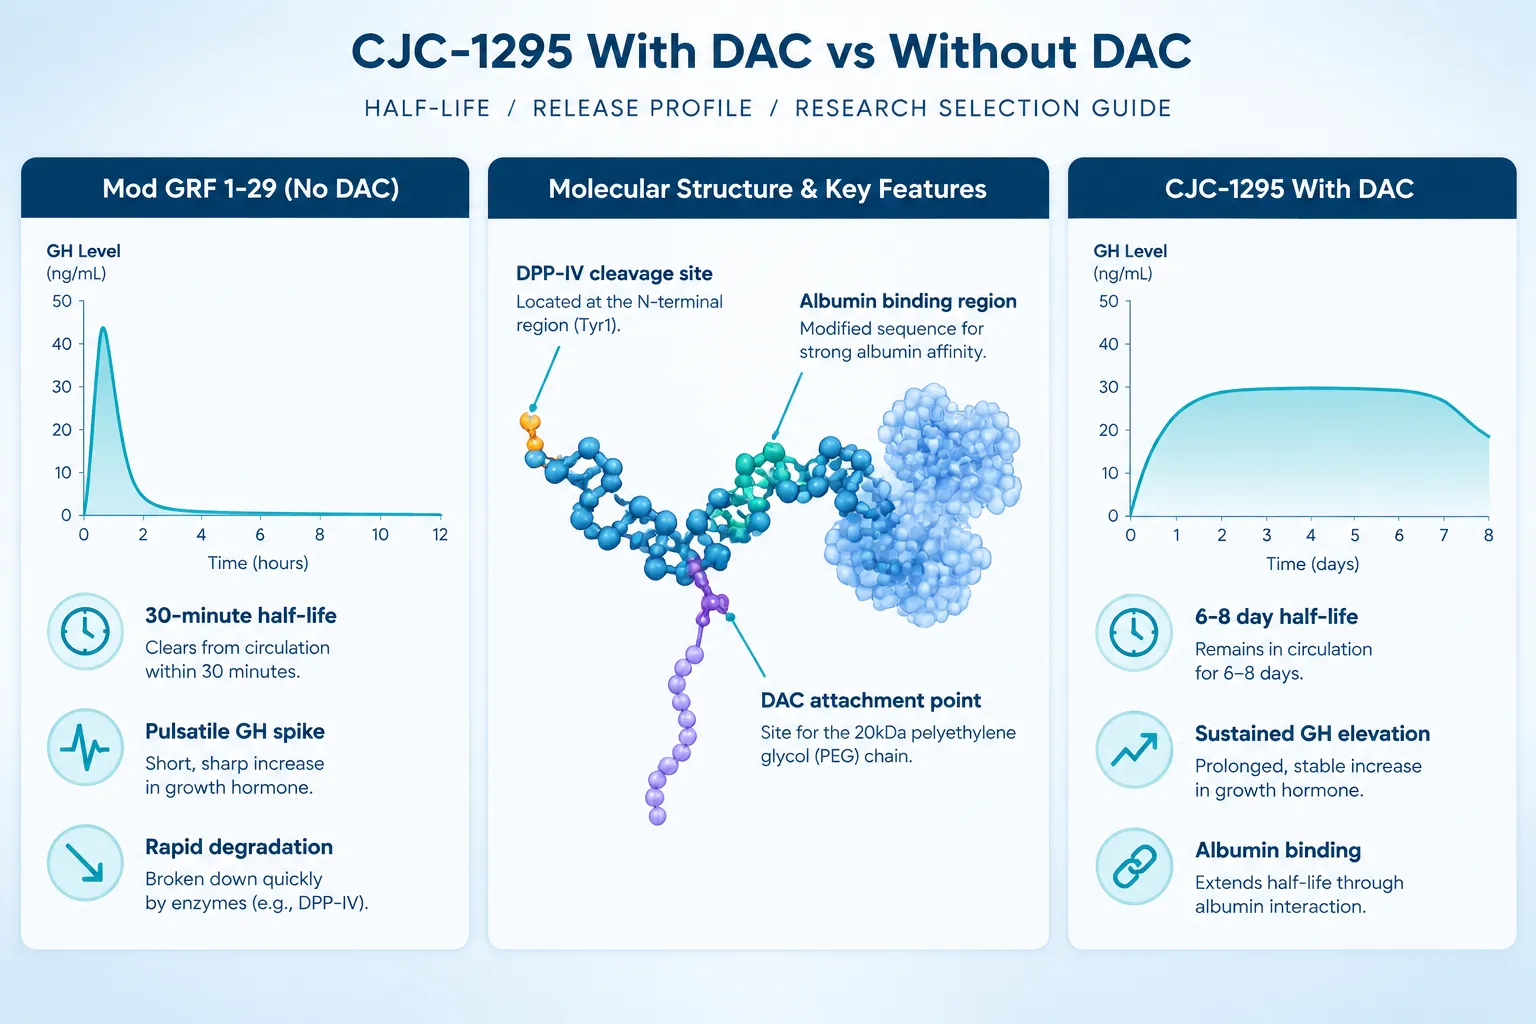
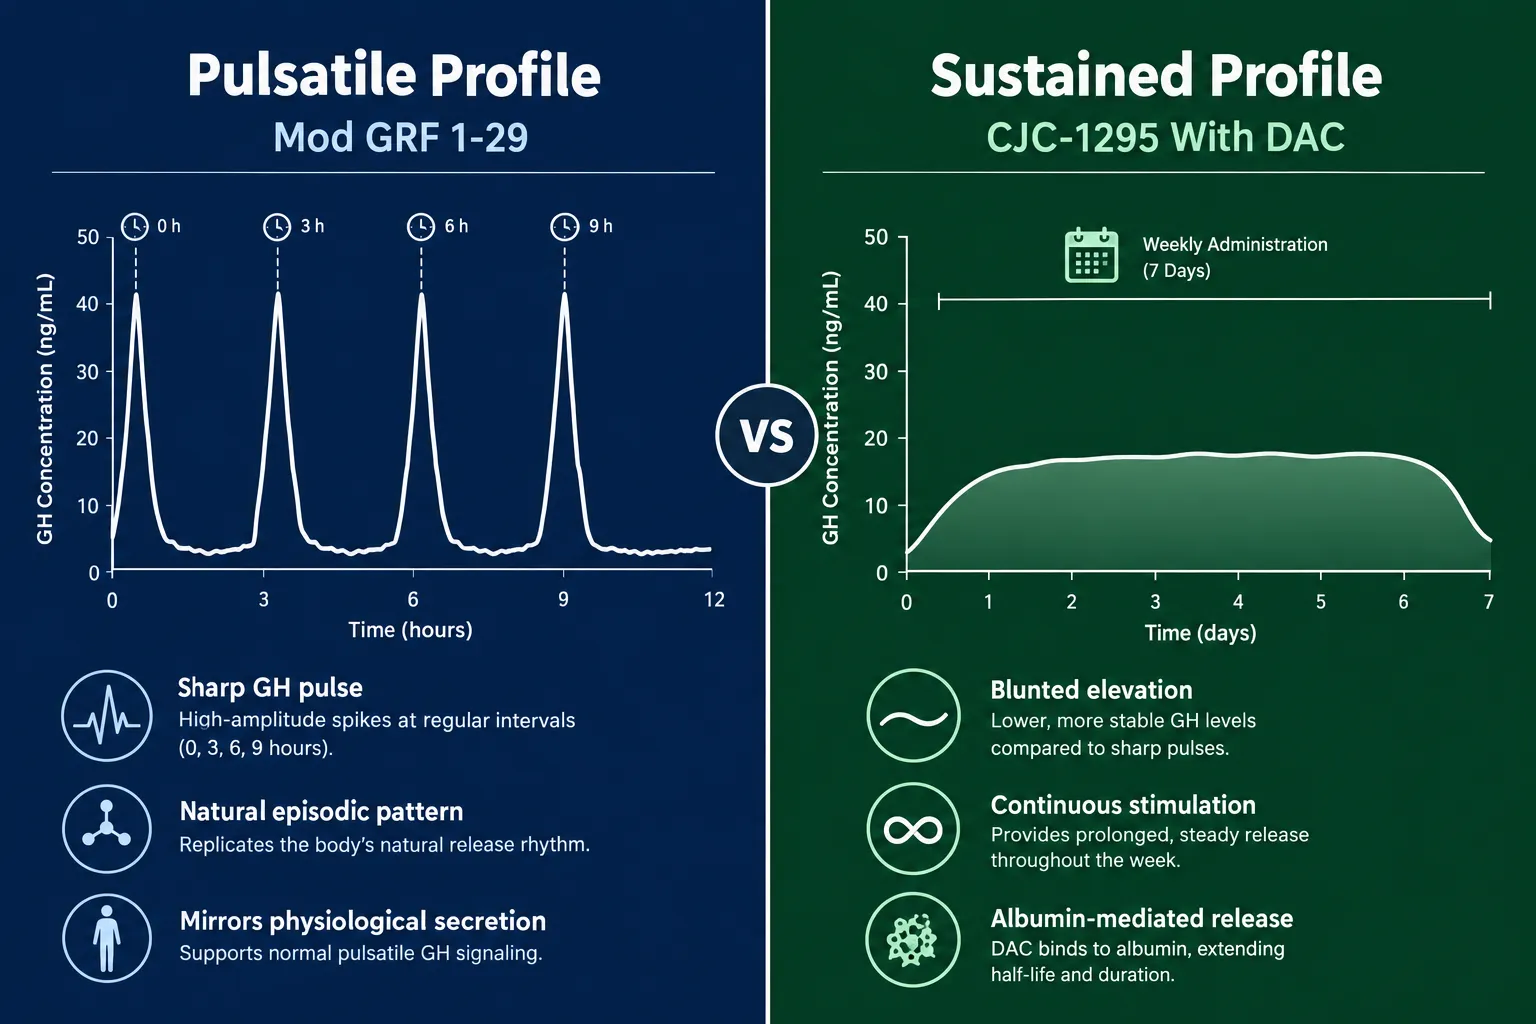
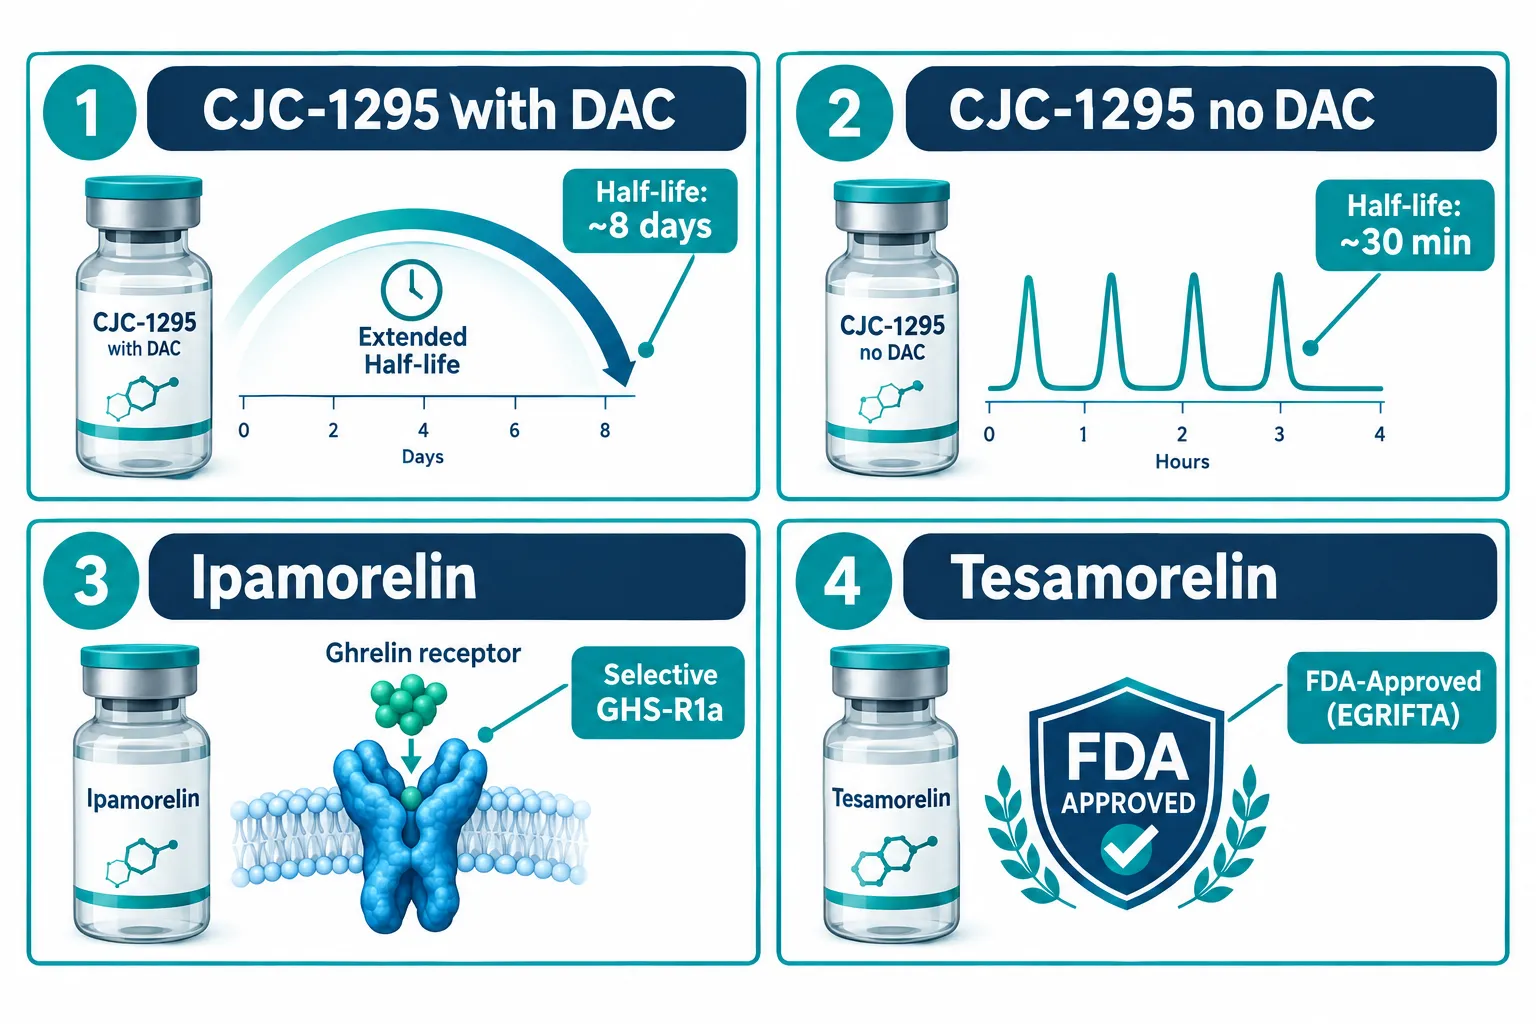
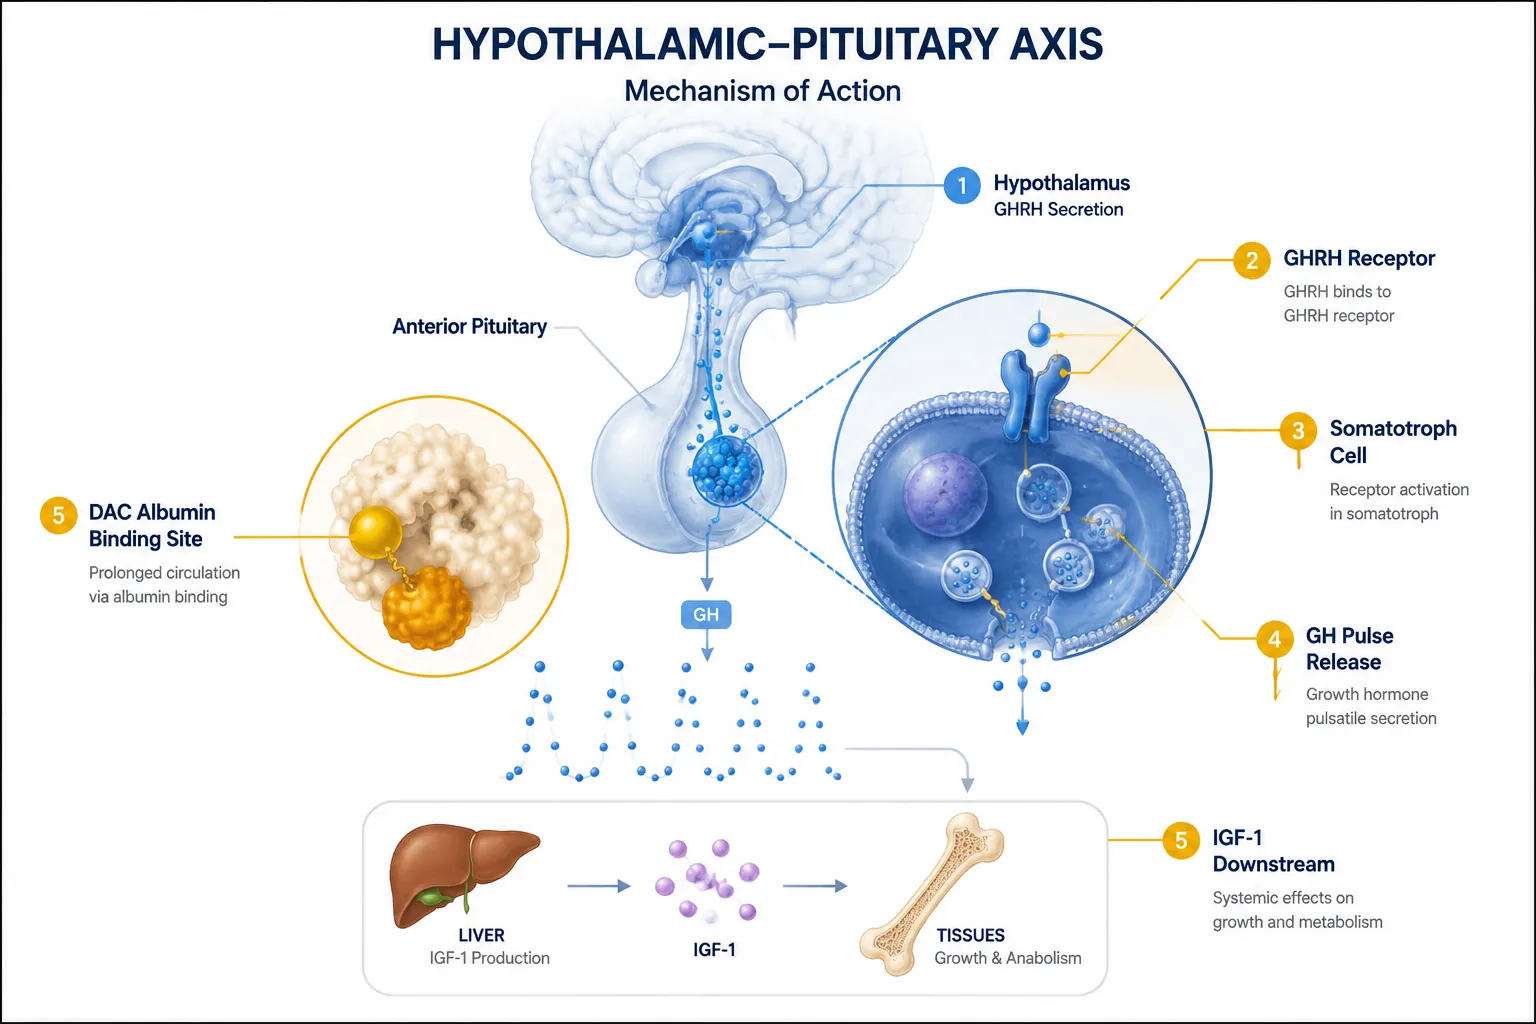
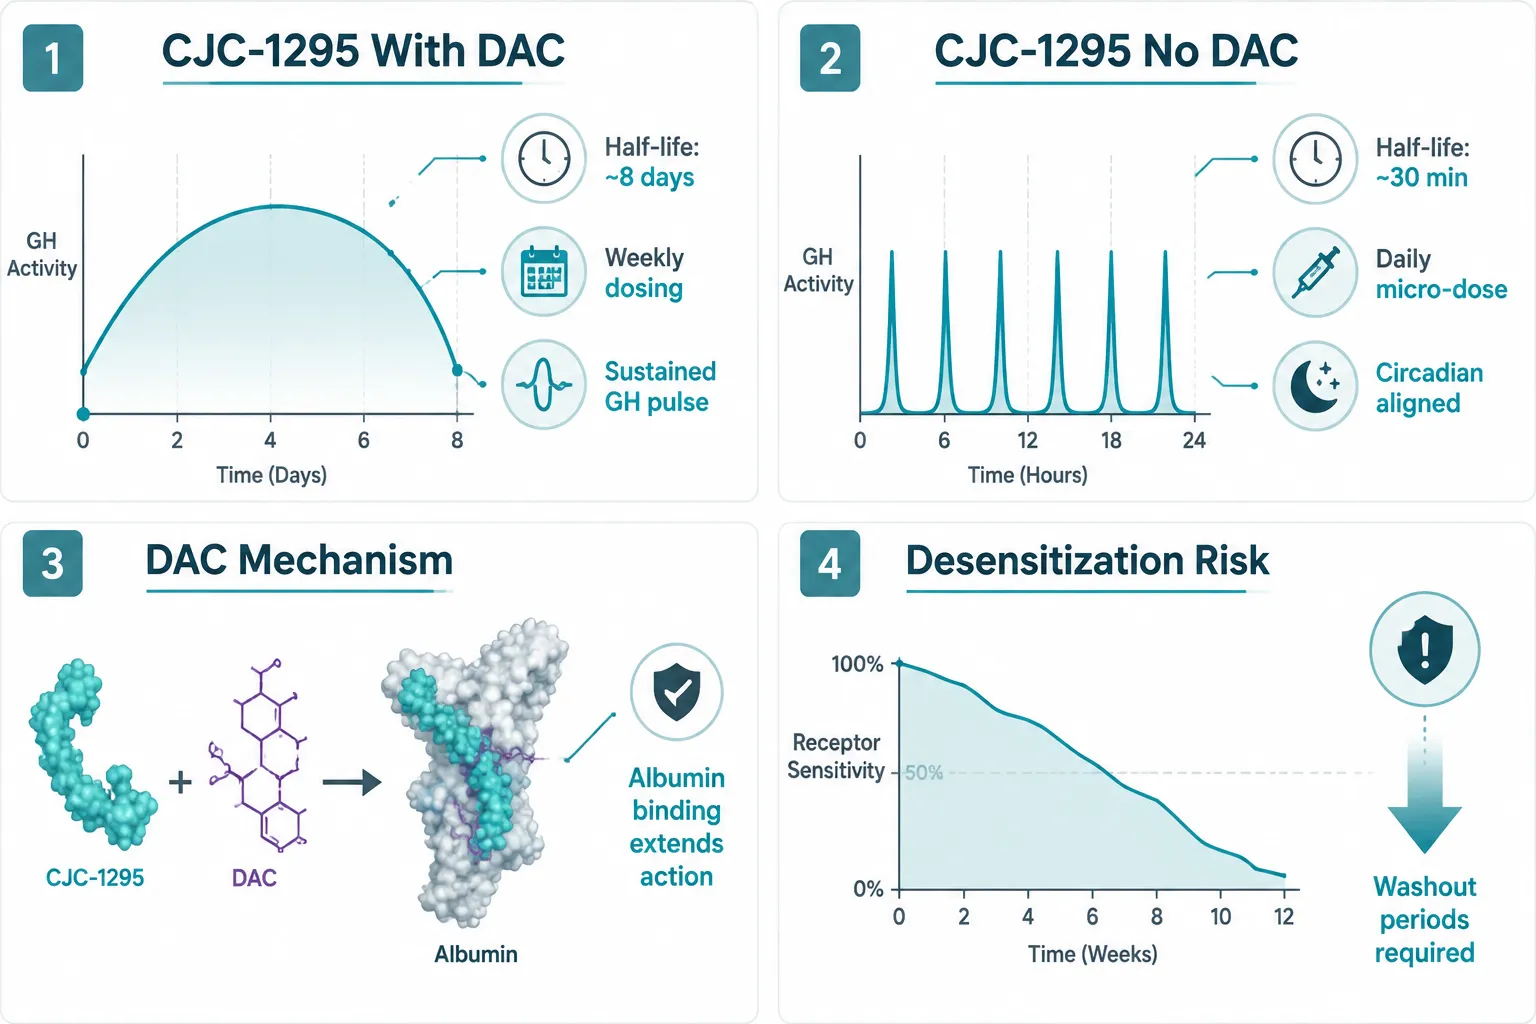
CJC-1295 with DAC uses a Drug Affinity Complex that binds covalently to circulating albumin, extending the half-life to approximately 6 to 8 days. This creates a continuous GHRH-receptor drive. The result is not a series of discrete GH pulses but a sustained elevation of GH secretion that, when measured at any single time point, can appear modest or even flat.

CJC-1295 without DAC (also called Modified GRF 1-29 or Mod GRF 1-29) clears within 30 minutes. It triggers a sharp, high-amplitude GH spike that subsides quickly. Miss that window, and the data shows nothing.

Feature With DAC Without DAC
Half-life ~6-8 days ~30 minutes
GH profile Sustained, low-amplitude Sharp, high-amplitude pulses
IGF-1 response Gradual multi-day elevation Rapid but short-lived
Sampling risk Misread as "flat" Missed entirely
Washout needed 3-4 weeks 4-6 hours

How Sampling Windows Change GH-Pulse and IGF-1 Research Outcomes

Research scientist reviewing GH sampling timeline and schedule

This is where CJC-1295 With DAC vs Without DAC: How Sampling Windows Change GH-Pulse and IGF-1 Research becomes an experimental design problem, not just a pharmacology question.

Sampling for the No-DAC Form

Because Mod GRF 1-29 produces a narrow pulse window, a single blood draw taken two hours post-administration will almost certainly land on the descending slope or the baseline. Research groups aiming to characterize pulse frequency and amplitude should use 20-minute overnight sampling intervals. This approach, originally validated in foundational GH-pulsatility studies, remains the gold standard for short-acting GHRH analogs.

Key design principles for no-DAC protocols:

  • Draw samples every 15 to 20 minutes for at least 8 hours
  • Time the administration precisely relative to the first sample
  • Avoid single-point or two-point draws, they are statistically unreliable for pulsatile endpoints
  • Use area-under-the-curve (AUC) calculations rather than peak-only readings

Sampling for the DAC Form

With the DAC variant, the opposite problem emerges. A researcher drawing blood at 30 minutes post-injection will capture an early phase that does not represent the compound's full effect. Conversely, a single draw at day 3 or day 7 may show only modest GH elevation, not because the compound is weak, but because continuous GHRH drive produces a "baseline elevation" rather than a true pulse.

"The distinction between baseline elevation and true loss of pulsatility is one of the most commonly misread findings in DAC-form research."

For DAC studies, IGF-1 is the more appropriate primary endpoint. IGF-1 integrates multi-day GH exposure and reflects cumulative secretion more accurately than any single GH draw. Teichman et al. pharmacokinetic data, which still underpins most IGF-1 expectations for this compound class, supports drawing IGF-1 at day 7 and day 14 post-administration for meaningful signal capture.

Researchers interested in combination protocols can also review the Tesamorelin, AOD9604, CJC-1295, and Ipamorelin 12mg blend and the Tesamorelin CJC-1295 Ipamorelin 12mg blend dosage resource for context on multi-peptide sampling considerations.


Designing Experiments That Avoid Sampling Bias

Step-by-step research design flow for CJC-1295 GH sampling

The absence of a published randomized head-to-head trial comparing DAC and no-DAC forms with harmonized sampling windows means researchers are currently working from indirect comparisons. That gap makes experimental design choices more consequential, not less.

Washout Planning

DAC washout requires a minimum of 3 to 4 weeks before crossover designs can begin. Residual albumin-bound compound continues to stimulate GHRH receptors long after the last administration. Failure to account for this creates carryover effects that inflate baseline IGF-1 in the second arm.

No-DAC washout is far shorter, typically 4 to 6 hours, but researchers should still confirm return to pre-study GH pulsatility patterns before beginning a new phase.

Endpoint Selection Framework

  • Primary endpoint for no-DAC: GH pulse amplitude and frequency via frequent serial sampling
  • Primary endpoint for DAC: IGF-1 at day 7 and day 14
  • Secondary endpoint for both: AUC calculations to normalize for inter-subject variability

For those studying related GHRH-receptor peptides alongside GH secretagogues, the safety considerations for combining Tesamorelin with CJC-1295 and Ipamorelin offers useful context on receptor interaction timelines.

A note on receptor down-regulation: 2026 industry analyses have raised questions about whether continuous DAC-driven stimulation leads to "GH exhaust" or receptor desensitization over extended protocols. The evidence remains speculative, but it reinforces the value of including washout periods and baseline re-checks in any multi-week design. Researchers sourcing compounds for these studies can reference the CJC-1295 IPA 10mg product page for purity and specification data.


Conclusion

The debate around CJC-1295 With DAC vs Without DAC: How Sampling Windows Change GH-Pulse and IGF-1 Research is ultimately a debate about matching measurement tools to the biology being studied. A sharp GH pulse cannot be captured with a sparse sampling schedule, and a sustained IGF-1 elevation cannot be evaluated with a single early draw.

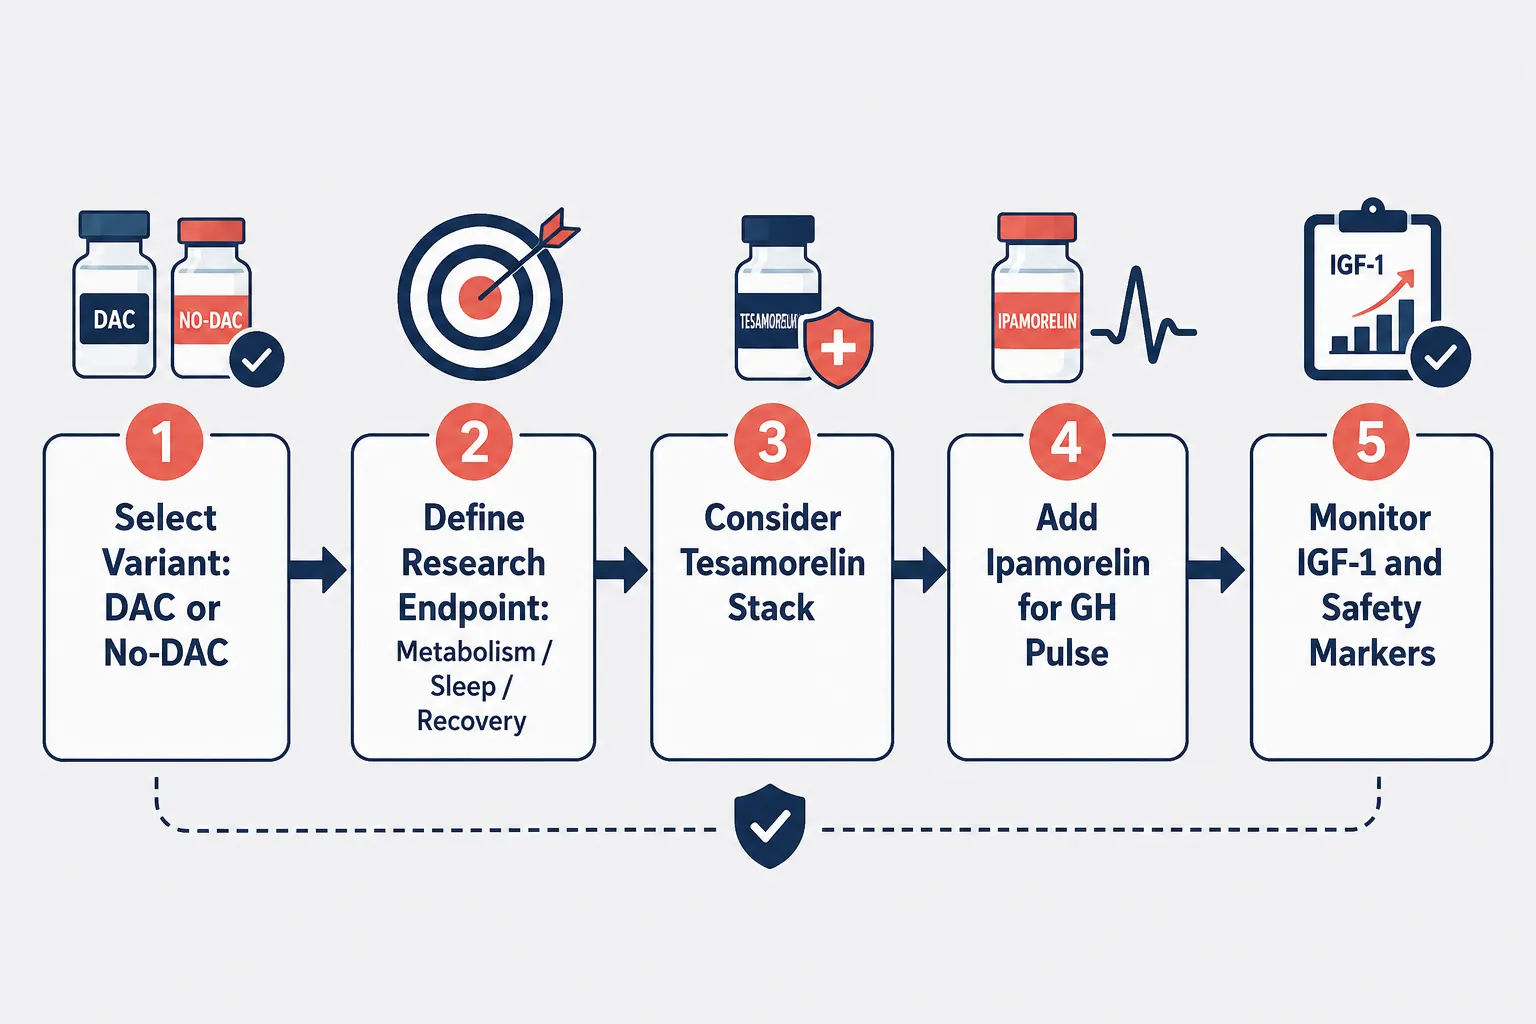
Actionable steps for researchers in 2026:

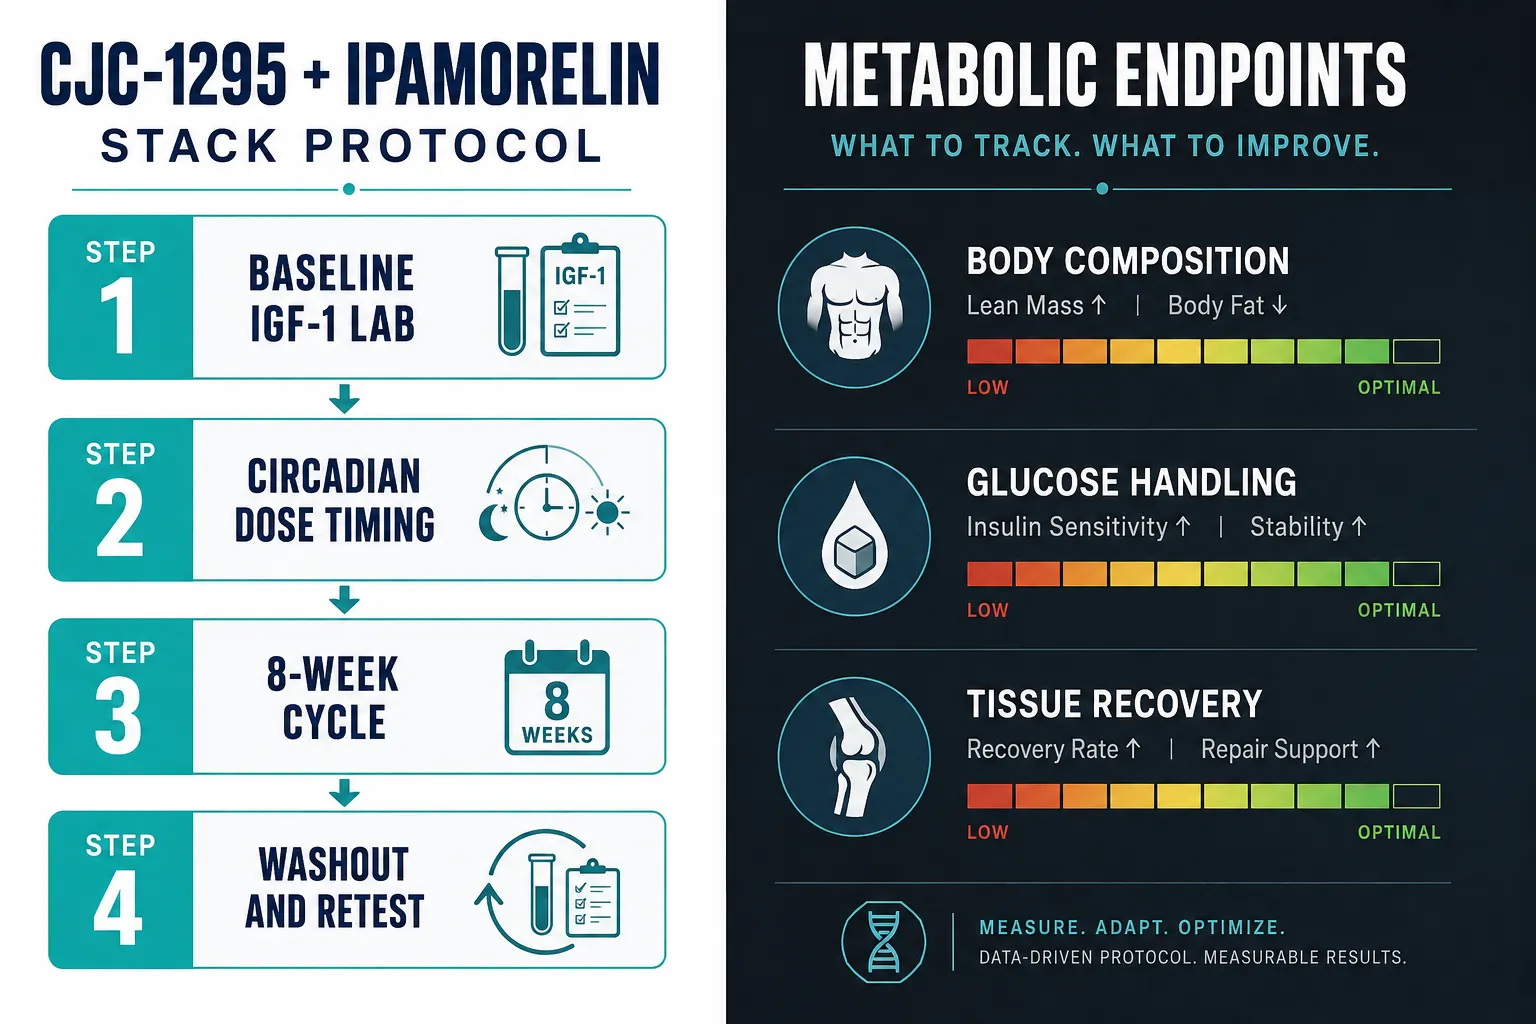
  1. Define the endpoint first, pulse characterization or integrated IGF-1 elevation, before selecting the compound form.
  2. For no-DAC analogs, commit to 15 to 20-minute serial sampling over at least 8 hours.
  3. For DAC forms, schedule IGF-1 draws at day 7 and day 14, and build in a 3 to 4-week washout before any crossover.
  4. Distinguish "baseline elevation" from "blunted pulsatility" in the interpretation phase, they are not the same finding.
  5. Document sampling timing with the same rigor applied to dosing, timing variability is a confounding variable, not a minor procedural note.

Rigorous sampling design is not a secondary concern. It is the mechanism by which the pharmacokinetic differences between these two compound forms become visible, or invisible, in the data.

https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 0 0 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-30 13:19:042026-09-30 13:19:04CJC-1295 With DAC vs Without DAC: How Sampling Windows Change GH-Pulse and IGF-1 Research
ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues

ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues

September 27, 2026/0 Comments/in Uncategorized/by

Nearly one billion adults worldwide live with hypertension, yet a growing number of researchers are simultaneously exploring growth-hormone secretagogue peptides whose hemodynamic effects remain poorly characterized. That overlap creates a real experimental design problem. When studying ACE inhibitors and research peptides, specifically designing blood-pressure controls around lisinopril and growth-hormone secretagogues, researchers must understand how ACE-pathway modulation shapes blood pressure, renal readouts, and fluid balance, and how those changes can confound or clarify CJC-1295, ipamorelin, and tesa experiments.

Key Takeaways

  • Lisinopril is a long-acting, evidence-backed ACE inhibitor with well-defined effects on blood pressure, cardiac events, and kidney function.
  • Growth-hormone secretagogues such as ipamorelin, CJC-1295, and tesa can cause fluid retention and potential blood-pressure elevation, particularly in stage 2 hypertension.
  • No rigorous human study has directly measured blood-pressure changes attributable to ipamorelin alone, creating a significant data gap.
  • ACE-pathway suppression alters aldosterone levels and glomerular filtration, which directly affects how renal endpoints are interpreted in peptide research.
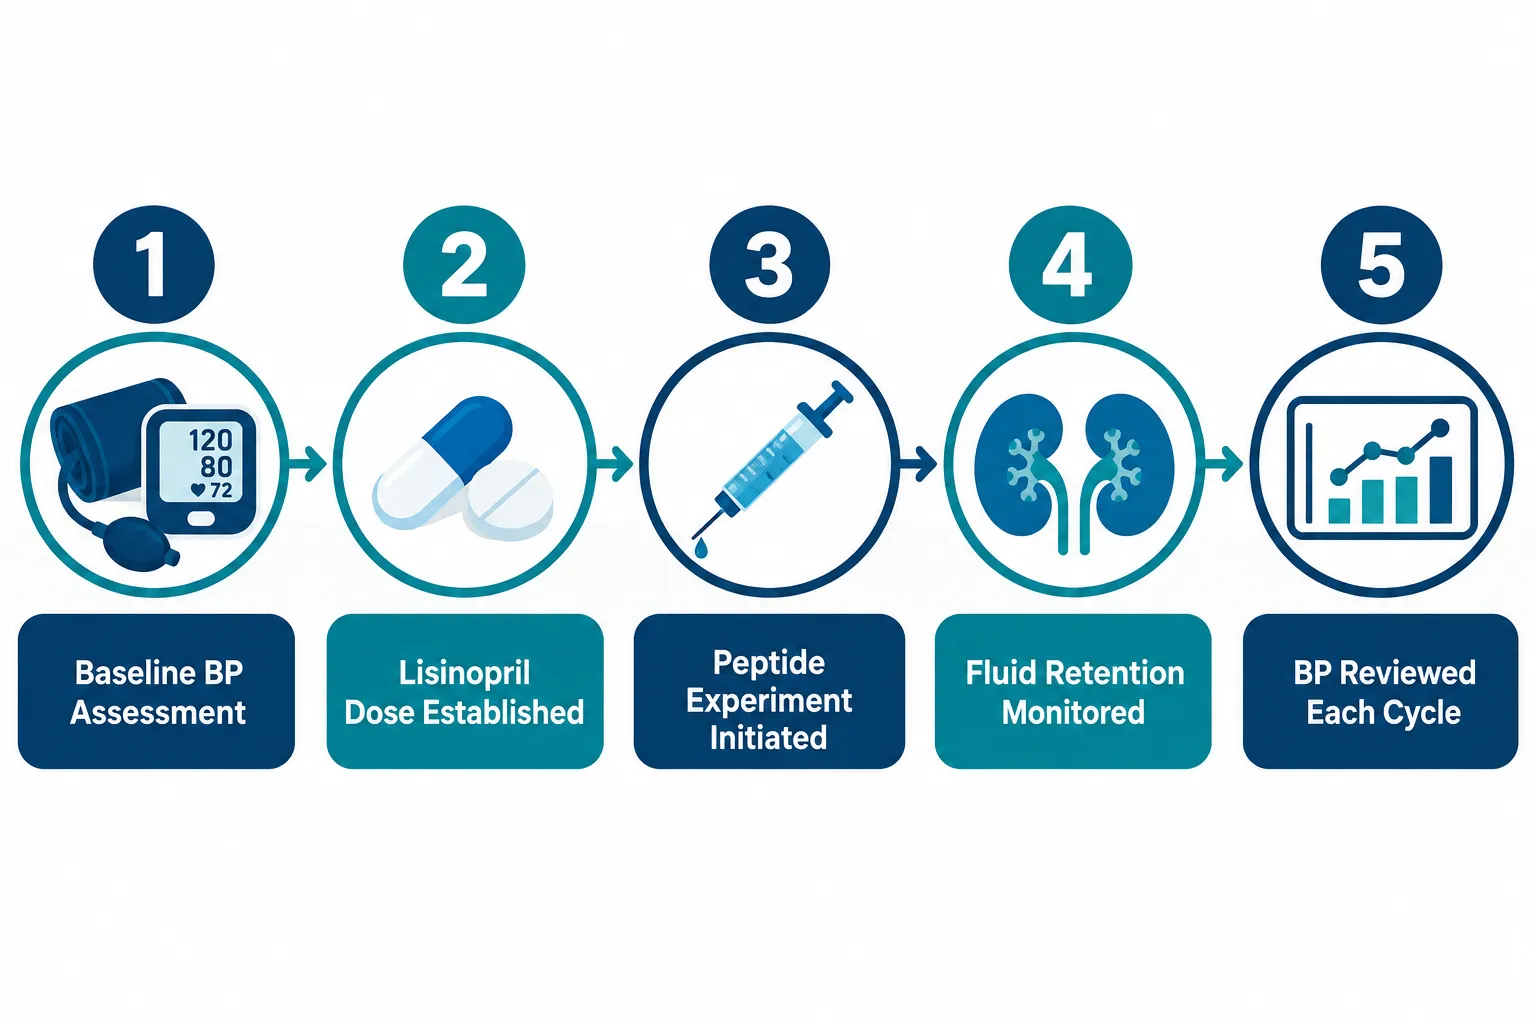
  • Designing valid research protocols requires establishing stable lisinopril dosing before introducing GH-axis peptides, then monitoring BP at every injection-period review.

How the ACE Pathway Controls Blood Pressure and Renal Readouts

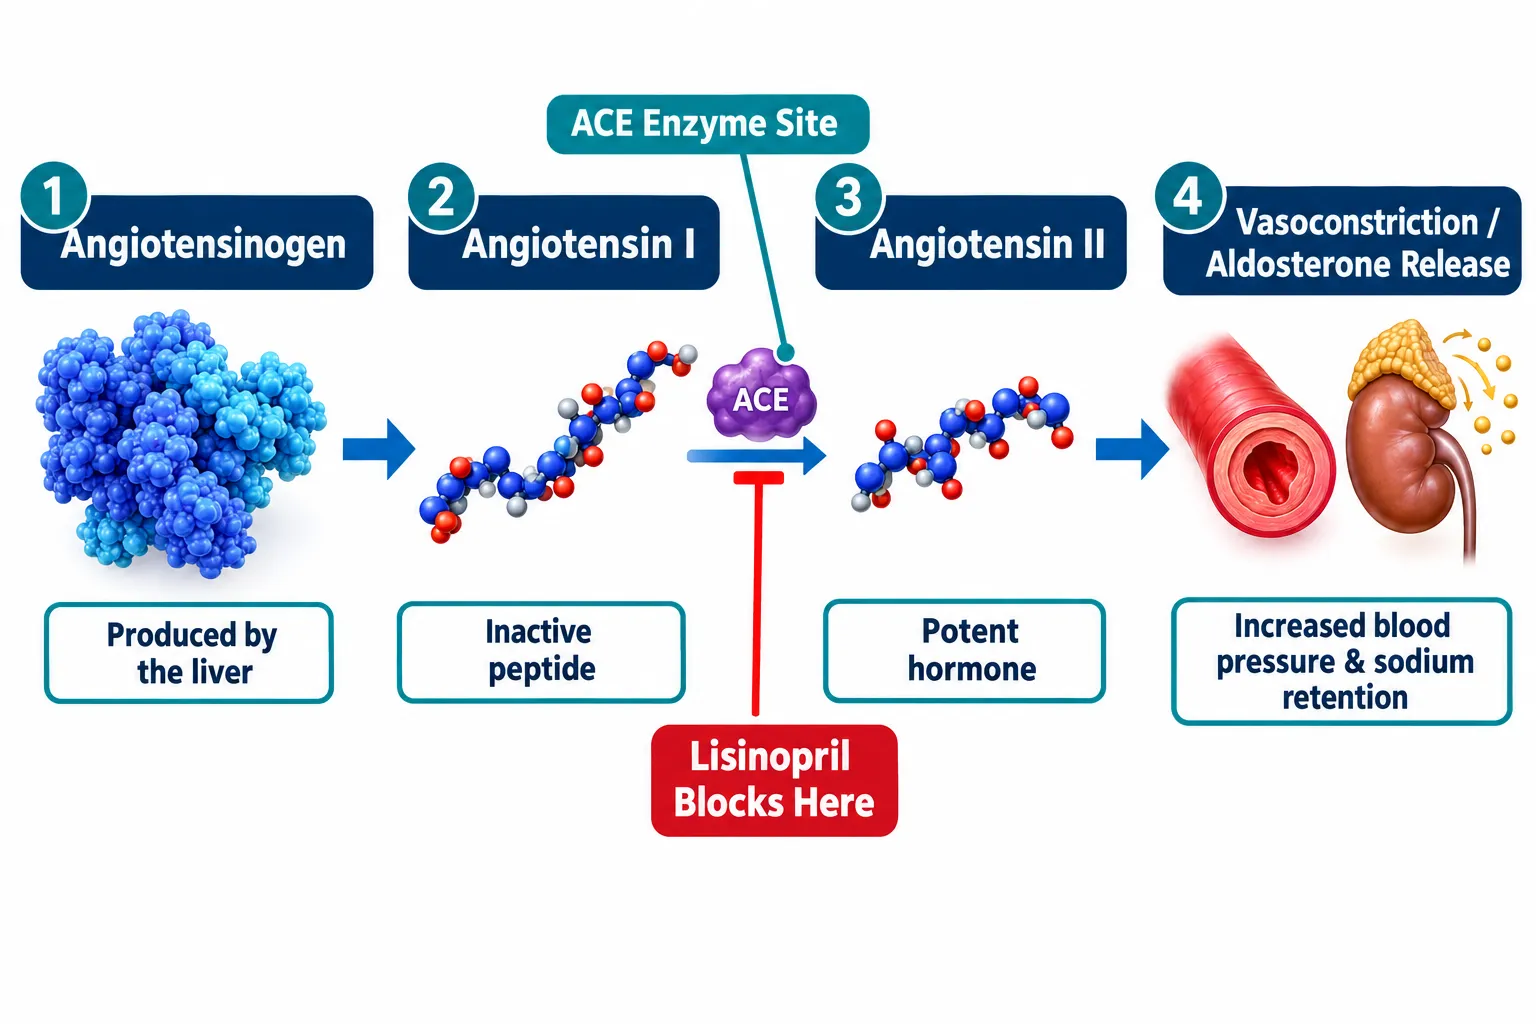
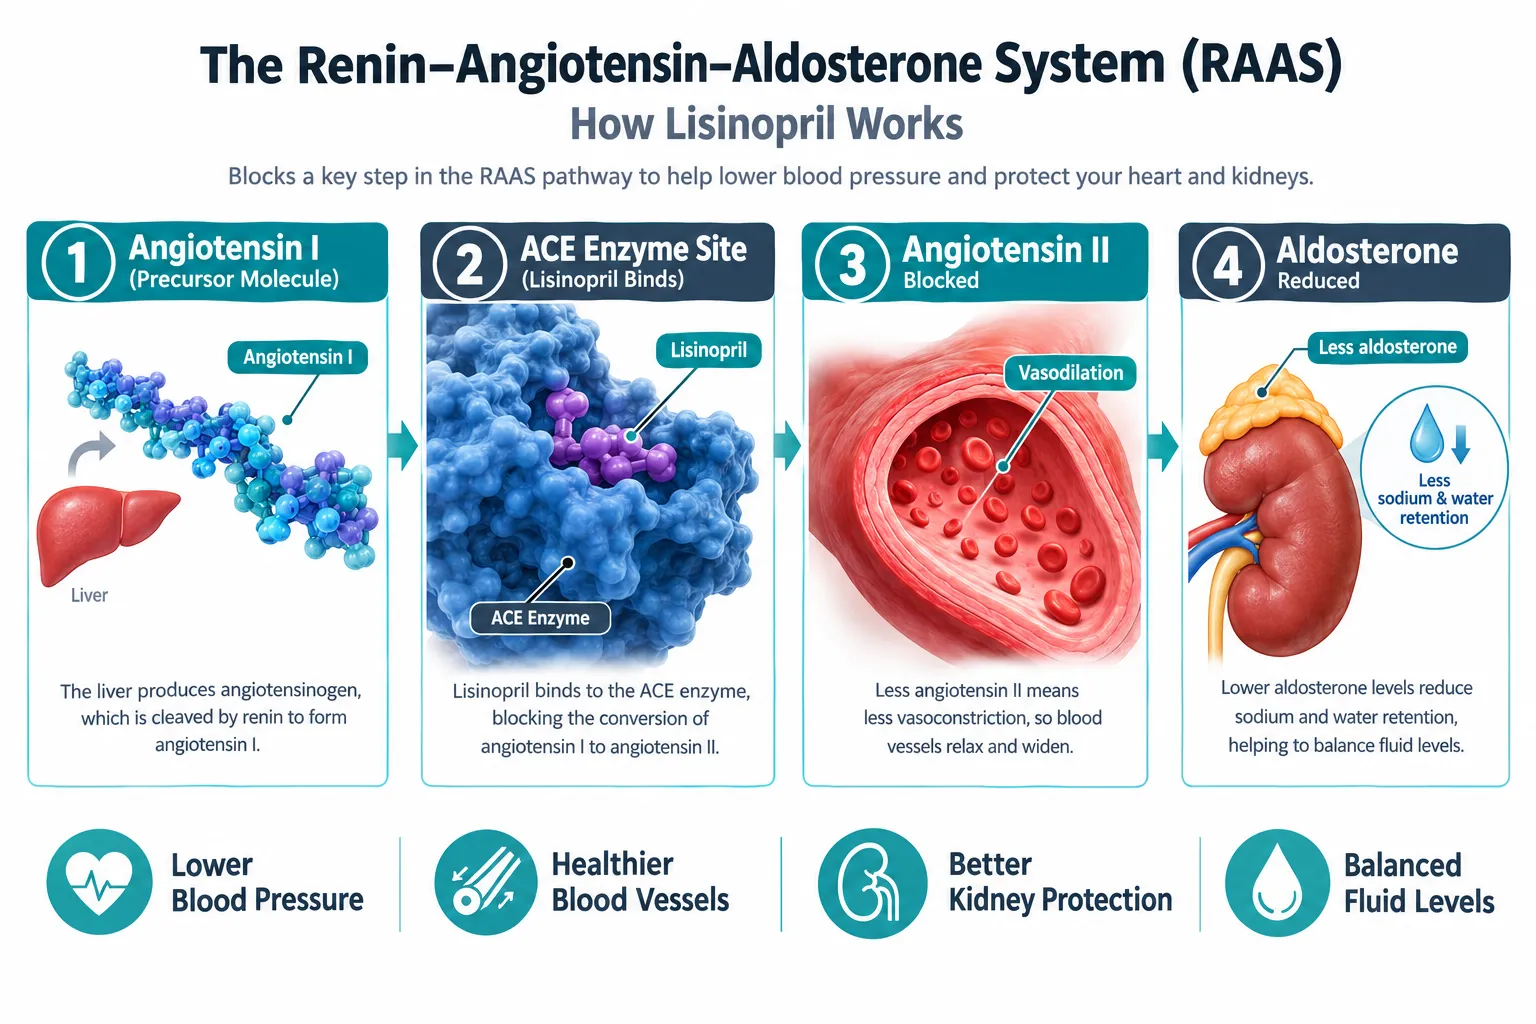
The renin-angiotensin-aldosterone system (RAAS) is the body's primary long-term blood-pressure regulator. Angiotensin-converting enzyme (ACE) converts angiotensin I into angiotensin II, a potent vasoconstrictor that also stimulates aldosterone release. Aldosterone drives sodium and water retention, raising blood volume and pressure.

How the ACE Pathway Controls Blood Pressure and Renal Readouts

Lisinopril blocks this conversion step directly. As an oral, long-acting ACE inhibitor, it is indicated for hypertension, heart failure, post-myocardial infarction management, and proteinuric diabetic kidney disease. Its pharmacological footprint extends well beyond simple vasodilation:

Effect Mechanism Research Relevance
Blood-pressure reduction Reduced angiotensin II, lower vascular resistance Establishes hemodynamic baseline
Natriuresis Decreased aldosterone, increased sodium excretion Alters fluid-balance readouts
Reduced GFR acutely Efferent arteriole dilation Affects creatinine and eGFR endpoints
Anti-proteinuric Reduced intraglomerular pressure Confounds albumin-to-creatinine ratio data

For any experiment measuring renal or cardiovascular endpoints, these effects are not background noise, they are active variables. A researcher who introduces a GH secretagogue without first stabilizing ACE inhibitor dosing will be unable to separate peptide-driven changes from ongoing RAAS modulation.


Clinical Evidence Anchoring Lisinopril as the Control Agent

Understanding the evidentiary weight behind lisinopril matters when selecting it as a research control. Its role in ACE inhibitors and research peptides protocols, designing blood-pressure controls around lisinopril and growth-hormone secretagogues, is justified by decades of outcome data, not convention alone.

Post-MI data: In the GISSI-3 trial, nearly 19,400 acute myocardial infarction patients were randomized in a factorial design. Lisinopril-treated patients experienced roughly an 11% lower risk of death at six weeks compared with controls (6.4% versus 7.2%), establishing short-term ACE inhibition as a mortality-reducing intervention after cardiac events.

Heart failure dosing: A study in over 3,100 chronic heart-failure patients followed for a median of 46 months found that high-dose lisinopril produced a 12% risk reduction in the combined endpoint of all-cause mortality and hospitalization, and a 24% reduction in heart-failure hospitalizations specifically, compared with low-dose therapy. This supports titrating toward higher target doses when tolerated.

Renal protection: The VA NEPHRON trial enrolled 1,448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratios, and reduced eGFR (30-89.9 mL/min), randomizing them to lisinopril or placebo on a background of losartan. This underscores lisinopril's role in intensive renal-risk management.

Key point: Because lisinopril independently alters urinary albumin excretion and eGFR, any peptide experiment using renal endpoints must document lisinopril dose stability for at least four to six weeks before baseline measurements are taken.

For researchers exploring peptide fundamentals, the Peptides 101 for Research-Use Only Buyers guide provides useful structural and mechanistic context.

Clinical Evidence Anchoring Lisinopril as the Control Agent


GH Secretagogues, Fluid Balance, and Blood-Pressure Risk

Growth-hormone secretagogues, including ipamorelin, CJC-1295, and tesa, stimulate the pituitary to release growth hormone, which in turn elevates IGF-1. This GH-axis activation carries hemodynamic consequences that directly complicate blood-pressure research design.

The fluid-retention problem: GH promotes sodium and water retention through IGF-1-mediated renal tubular effects. In a subject already on lisinopril, which promotes natriuresis, the opposing forces can mask or amplify fluid shifts, making weight and edema measurements unreliable without careful protocol design.

Blood-pressure uncertainty: No identified human study has directly measured blood-pressure changes attributable to ipamorelin alone. That data gap is critical. Safety reviews in 2026 flag that GH-axis secretagogues can raise blood pressure through both fluid retention and sympathomimetic effects of elevated GH. Specific concern exists at stage 2 hypertension (systolic BP above 160 mmHg), where persistent elevation refractory to standard management is considered a serious adverse event warranting reconsideration of peptide use.

Practical monitoring thresholds:

  • Blood pressure should be checked at every injection-period review
  • Persistent systolic BP above 160 mmHg flags a serious adverse event
  • Patients with cardiovascular disease require cardiologist consultation before GH secretagogue exposure
  • Fluid retention should be tracked via daily weight and ankle circumference measurements

Researchers interested in the IPA Sermorelin stack research protocols will find these monitoring principles directly applicable. For peptide sourcing considerations, the best peptide supplier resource is worth reviewing alongside purity documentation.

GH Secretagogues, Fluid Balance, and Blood-Pressure Risk


Designing a Valid Research Protocol

Translating the above into a workable experimental framework requires sequencing interventions carefully. The core principle in ACE inhibitors and research peptides design, blood-pressure controls around lisinopril and growth-hormone secretagogues, is that the ACE inhibitor must be the stable foundation, not an active variable.

Recommended sequencing:

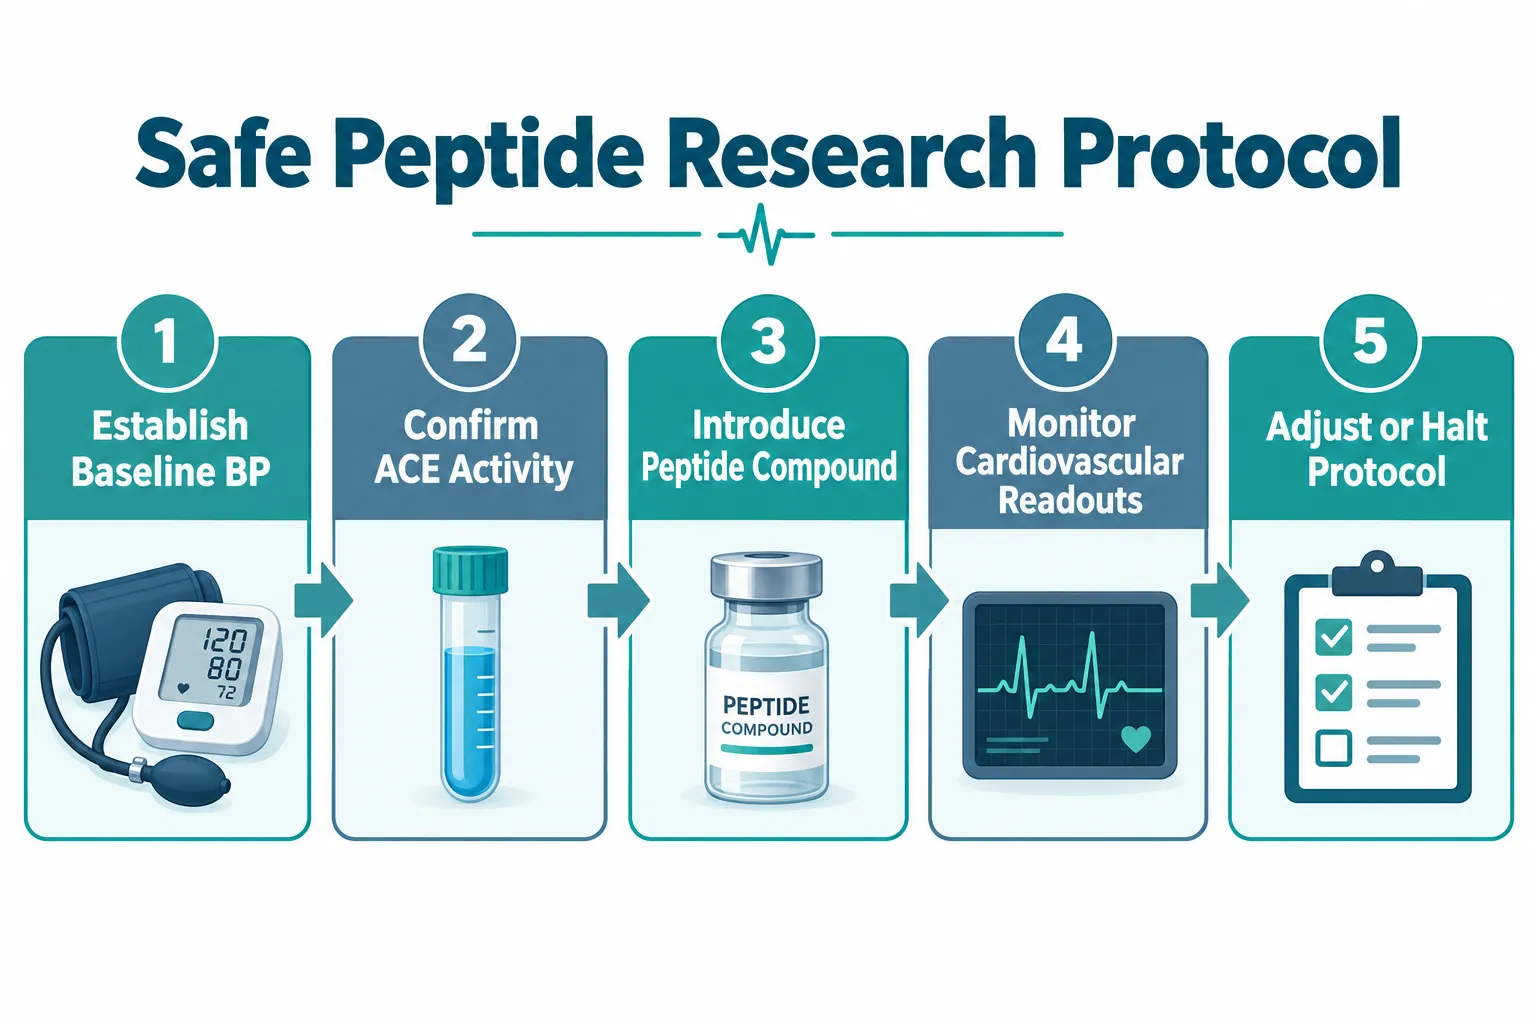
  1. Establish baseline hemodynamics, Record resting BP, eGFR, urinary albumin-to-creatinine ratio, and body weight before any intervention.
  2. Stabilize lisinopril dose, Allow four to six weeks at target dose with three consecutive BP readings within 10 mmHg of each other before proceeding.
  3. Document renal endpoints at steady state, Creatinine, eGFR, and urinary albumin reflect the lisinopril-stabilized baseline, not a moving target.
  4. Introduce the GH secretagogue, Begin ipamorelin, CJC-1295, or tesa at the lowest research dose.
  5. Monitor BP at every injection period, Flag any systolic reading above 160 mmHg as a protocol-defined serious event.
  6. Track fluid balance independently, Daily weight, edema scoring, and sodium intake logs separate peptide-driven fluid shifts from RAAS modulation.

Researchers studying mitochondrial or cytoprotective peptides alongside cardiovascular endpoints may also find the synergy of LL-37 and SS-31 research relevant, as SS-31 has distinct renal mitochondrial effects that interact with RAAS-modulated tissue. Similarly, SS-31 peptide benefits documentation provides useful comparative context when designing multi-peptide cardiovascular studies.

For researchers sourcing MOTS-c or related metabolic peptides alongside GH secretagogues, the MOTS-c peptide category offers additional product and mechanism information.


Conclusion

Designing rigorous blood-pressure controls in peptide research is not optional, it is the difference between interpretable data and noise. Lisinopril's well-characterized effects on RAAS, fluid balance, and renal endpoints make it a logical anchor for cardiovascular control arms, but only when its dose is stabilized before GH secretagogue introduction. Ipamorelin, CJC-1295, and tesa all carry real, if incompletely quantified, risks of fluid retention and blood-pressure elevation that can obscure experimental signals or create genuine safety events.

Actionable next steps for researchers in 2026:

  • Audit existing protocols to confirm lisinopril dose stability windows are documented before baseline renal measurements
  • Add systolic BP above 160 mmHg as a pre-specified serious adverse event criterion in any GH secretagogue study
  • Track fluid balance with daily weight logs, not just clinical BP readings
  • Consult cardiology input for any subject with pre-existing cardiovascular disease before GH-axis peptide exposure
  • Review purity certificates for all research peptides to ensure experimental variables are limited to pharmacology, not contaminant effects
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/ace-inhibitors-and-research-peptides-designing-blood-pressure-controls-around-li.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-27 13:03:392026-09-27 13:03:39ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues
CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation

CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation

September 25, 2026/0 Comments/in Uncategorized/by

A single amino acid modification, the Drug Affinity Complex (DAC), extends CJC-1295's plasma half-life from roughly 30 minutes to approximately six to eight days. That difference is not merely pharmacokinetic trivia. It reshapes every decision a researcher makes: when to draw blood, how long to wait before the next treatment cycle, and whether an observed IGF-1 signal belongs to the compound or to residual accumulation from a prior dose. Understanding CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation is therefore foundational to producing reproducible, attributable preclinical data.

Key Takeaways

  • CJC-1295 without DAC has a half-life near 30 minutes, making it ideal for studying acute, pulsatile GH release; CJC-1295 with DAC sustains elevated GH and IGF-1 for days to weeks.
  • Sampling windows must be matched to the compound's kinetic profile, mismatched timing leads to missed peaks or inflated baseline readings.
  • Washout for DAC-containing protocols requires a minimum of four to six weeks in rodent models to avoid carryover confounding.
  • IGF-1 attribution is the central interpretive challenge: sustained DAC exposure elevates tonic IGF-1, while the non-DAC form produces transient pulses that are easy to miss without frequent sampling.
  • Study design choices, dose interval, sample frequency, and washout length, differ substantially between the two forms and must be pre-specified in the protocol.

Half-Life Determines Everything Downstream

Half-Life Determines Everything Downstream

The pharmacokinetic contrast between the two forms is the logical starting point because every downstream design decision flows from it. CJC-1295 without DAC is a modified GHRH analogue that resists enzymatic cleavage long enough to reach pituitary receptors but is cleared within one to two hours in most rodent models. Its action is therefore discrete and pulse-like, closely mirroring endogenous GHRH activity.

CJC-1295 with DAC covalently binds to circulating albumin through its maleimido-propionyl group. This albumin linkage creates a depot effect, releasing active peptide slowly over days. In rat models, a single subcutaneous dose produces measurable GH elevation for up to five days and elevated IGF-1 for seven to ten days. The practical consequence is that a researcher who draws a single blood sample at 24 hours post-dose will capture very different biological states depending on which form was used.

For researchers exploring multi-peptide combinations, the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend illustrates how stacking long- and short-acting GHRH analogues complicates attribution further, reinforcing the need for precise kinetic mapping before interpreting outcomes.


Sampling Windows in Cell and Animal Studies: Matching Timing to Kinetics

Getting sampling windows right is where most preclinical CJC-1295 studies succeed or fail. The two forms demand fundamentally different schedules.

Without DAC: High-Frequency, Narrow Windows

Because the non-DAC form acts within minutes and clears rapidly, meaningful GH sampling must occur within 15 to 45 minutes post-administration in rodent models. A single time-point study will almost always underestimate peak GH. Recommended practice calls for serial sampling at 15, 30, 60, and 120 minutes to capture the full pulse shape. IGF-1, which responds more slowly to GH stimulation, should be sampled at 4, 8, and 24 hours to capture the downstream hepatic response.

Cell culture studies using the non-DAC form face an analogous challenge: peptide degradation in serum-containing media can reduce effective concentration within hours, so dosing intervals and media refresh schedules must be tightly controlled.

With DAC: Extended Windows, Accumulation Awareness

For the DAC form, single time-point sampling at 24 or 48 hours post-dose is more defensible, but researchers must account for accumulation across repeated doses. In a weekly dosing protocol over four weeks, plasma concentrations do not reach steady state until approximately the third dose. This means IGF-1 readings taken during weeks one and two reflect rising exposure, not steady-state biology. Comparing week-one IGF-1 to week-four IGF-1 without acknowledging this trajectory is a common interpretive error.

Recommended sampling in repeated-dose rodent studies with the DAC form:

  • Trough samples immediately before each dose (to track accumulation)
  • Peak samples 24 to 48 hours after each dose
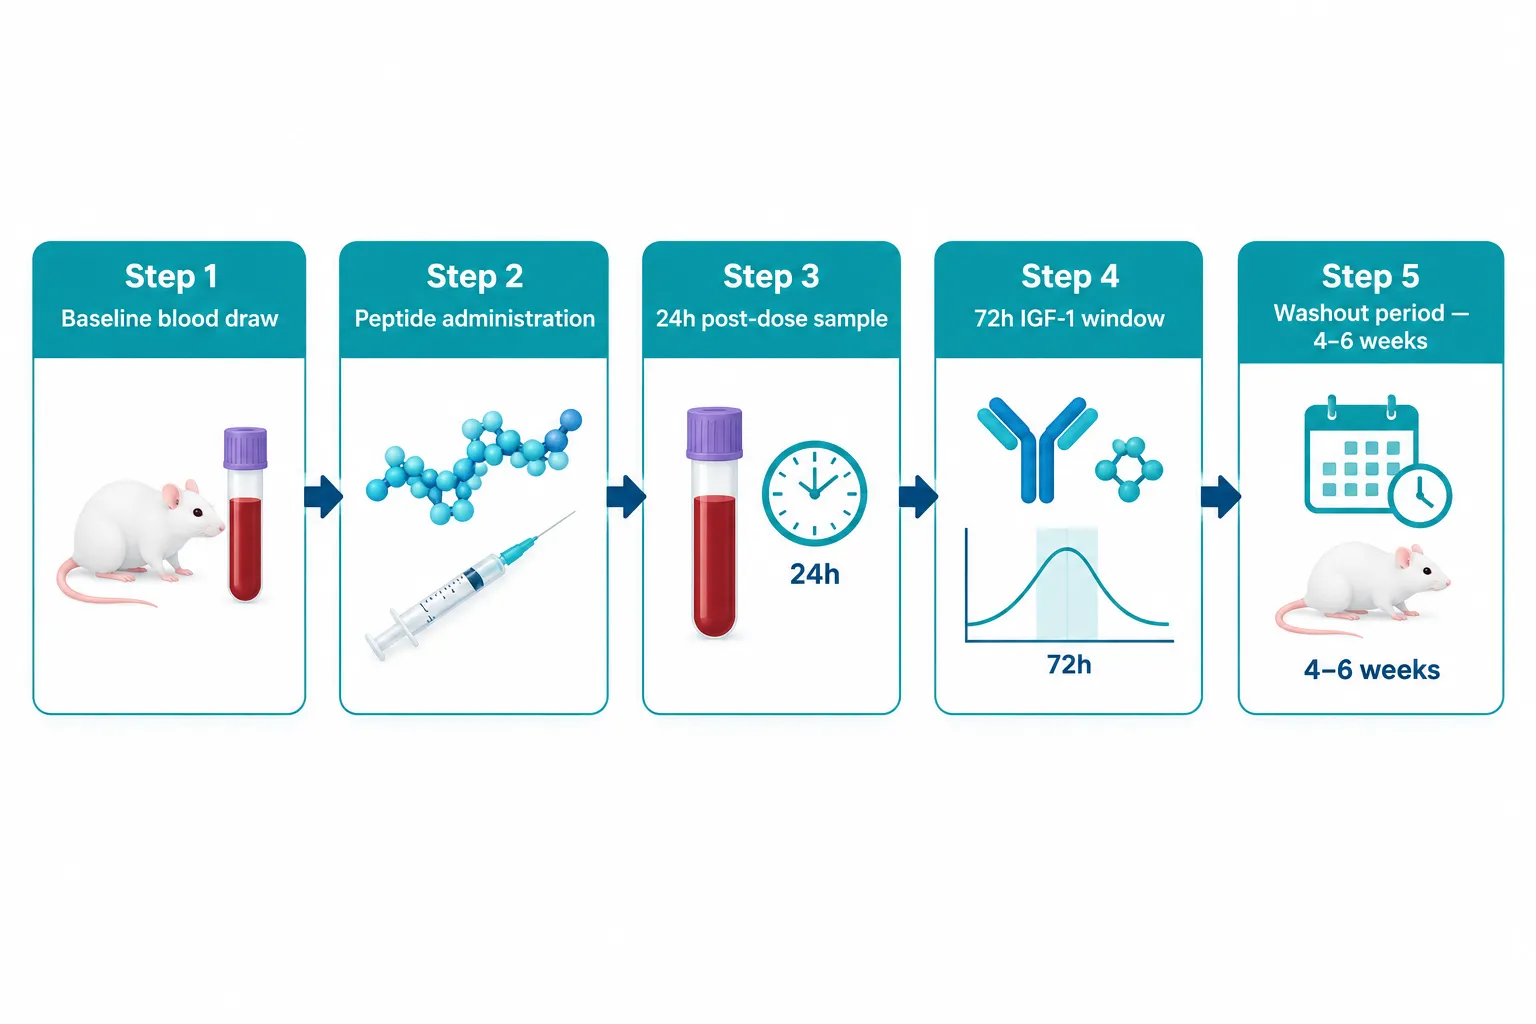
  • IGF-1 at 72 hours post-dose, where the signal is most stable
  • A terminal bleed at least seven days after the final dose to distinguish residual compound from true washout baseline

For those working with related combination protocols, the Sermorelin, Ipamorelin, and CJC-1295 blend offers context on how multiple secretagogues interact when sampling schedules must account for overlapping kinetic profiles.


Washout Design and IGF-1 Interpretation

Washout Design and IGF-1 Interpretation

Washout is arguably the most underspecified element in published CJC-1295 animal studies. A compound with a six-to-eight-day half-life requires approximately five half-lives, roughly 30 to 40 days, to fall below 5% of peak plasma concentration. In practice, most expert guidance as of 2026 recommends a minimum four-to-six-week washout in rodent models before a crossover arm or a new treatment cycle begins.

Shorter washouts produce carryover elevation of IGF-1 that can be misattributed to a new intervention. This is particularly problematic in crossover designs where the DAC form is tested first.

Attributing GH Pulsatility vs. Sustained Elevation

The interpretive challenge is not just about timing, it is about biology. The non-DAC form preserves the pulsatile nature of GH secretion. Studies examining GH-dependent cellular processes such as lipolysis, protein synthesis, or IGF-1 receptor upregulation benefit from this pulsatility because it more closely models physiological signaling. The DAC form, by contrast, creates a tonic elevation that may saturate GH receptors and alter downstream sensitivity over time.

"Sustained GH elevation and pulsatile GH elevation are not interchangeable experimental conditions, they activate overlapping but distinct receptor dynamics."

Researchers must therefore specify in their protocols whether the biological question requires pulsatile or sustained GH exposure, and select the appropriate form accordingly. Mixing the two forms within a single study without a full washout between them produces data that cannot be cleanly attributed to either kinetic profile.

For additional context on how CJC-1295 is used alongside complementary peptides in research settings, the Tesamorelin, AOD9604, CJC-1295, and Ipamorelin 12mg blend page provides relevant formulation background. Similarly, researchers comparing secretagogue safety profiles may find the discussion on combining Tesamorelin with CJC Ipamorelin useful for contextualizing multi-compound study designs.


Practical Protocol Recommendations

Practical Protocol Recommendations

The following framework consolidates current best-practice guidance for preclinical researchers as of 2026:

Parameter Without DAC With DAC
GH sampling window 15-60 min post-dose 24-48 h post-dose
IGF-1 sampling window 4-24 h post-dose 48-72 h post-dose
Steady-state onset Single dose ~3rd dose (weekly protocol)
Minimum washout 48-72 hours 4-6 weeks
Crossover design risk Low High without full washout

For dose-ranging studies, the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend dosage guide and the corresponding dose reference offer practical starting points when CJC-1295 is part of a multi-peptide protocol.

Key protocol checkpoints:

  • Pre-specify whether the study question requires pulsatile or tonic GH exposure
  • Document accumulation phase separately from steady-state phase in multi-dose designs
  • Include a satellite group for washout verification if the study uses a crossover design
  • In cell studies, refresh media at intervals matched to the peptide's degradation rate in the specific media formulation used

Conclusion

The choice between CJC-1295 with DAC and without DAC is not simply a matter of dosing convenience, it is a fundamental experimental variable that determines when to sample, how long to wait, and how to interpret every GH or IGF-1 data point the study generates. Researchers who treat the two forms as interchangeable risk producing results that are either uninterpretable or actively misleading.

Actionable next steps for preclinical researchers:

  1. Define the biological question first, pulsatile or sustained GH exposure, then select the compound form that matches it.
  2. Build sampling schedules around the compound's actual kinetic profile, not convenience time-points.
  3. Enforce a minimum four-to-six-week washout for any DAC-containing protocol before a crossover or repeat cycle.
  4. Track trough concentrations across a multi-dose DAC study to confirm when steady state is reached before drawing mechanistic conclusions.
  5. Report the form used, the sampling schedule, and the washout length explicitly in methods sections so findings can be accurately compared across studies.

Rigorous attention to these design elements is what separates publishable, reproducible CJC-1295 research from data that raises more questions than it answers.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cjc-1295-with-dac-vs-without-dac-in-cell-and-animal-studies-sampling-windows-was.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-25 13:03:292026-09-25 13:03:29CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation
Growth-Hormone Secretagogue Research Design: Comparing Tesamorelin, CJC-1295, Ipamorelin, and Sermorelin by Signal Duration

Growth-Hormone Secretagogue Research Design: Comparing Tesamorelin, CJC-1295, Ipamorelin, and Sermorelin by Signal Duration

September 24, 2026/0 Comments/in Uncategorized/by

Fewer than 4% of a subcutaneous tesa dose reaches systemic circulation, yet that brief plasma exposure, peaking in under 10 minutes and clearing within roughly half an hour, is enough to drive measurable reductions in visceral fat in HIV-associated lipodystrophy. That pharmacokinetic reality sits at the core of Growth-Hormone Secretagogue Research Design: Comparing Tesamorelin, CJC-1295, Ipamorelin, and Sermorelin by Signal Duration: the duration of a peptide's plasma signal is not a side note, it is the primary variable that determines assay timing, endpoint selection, and the validity of any IGF-1 interpretation.

Key Takeaways

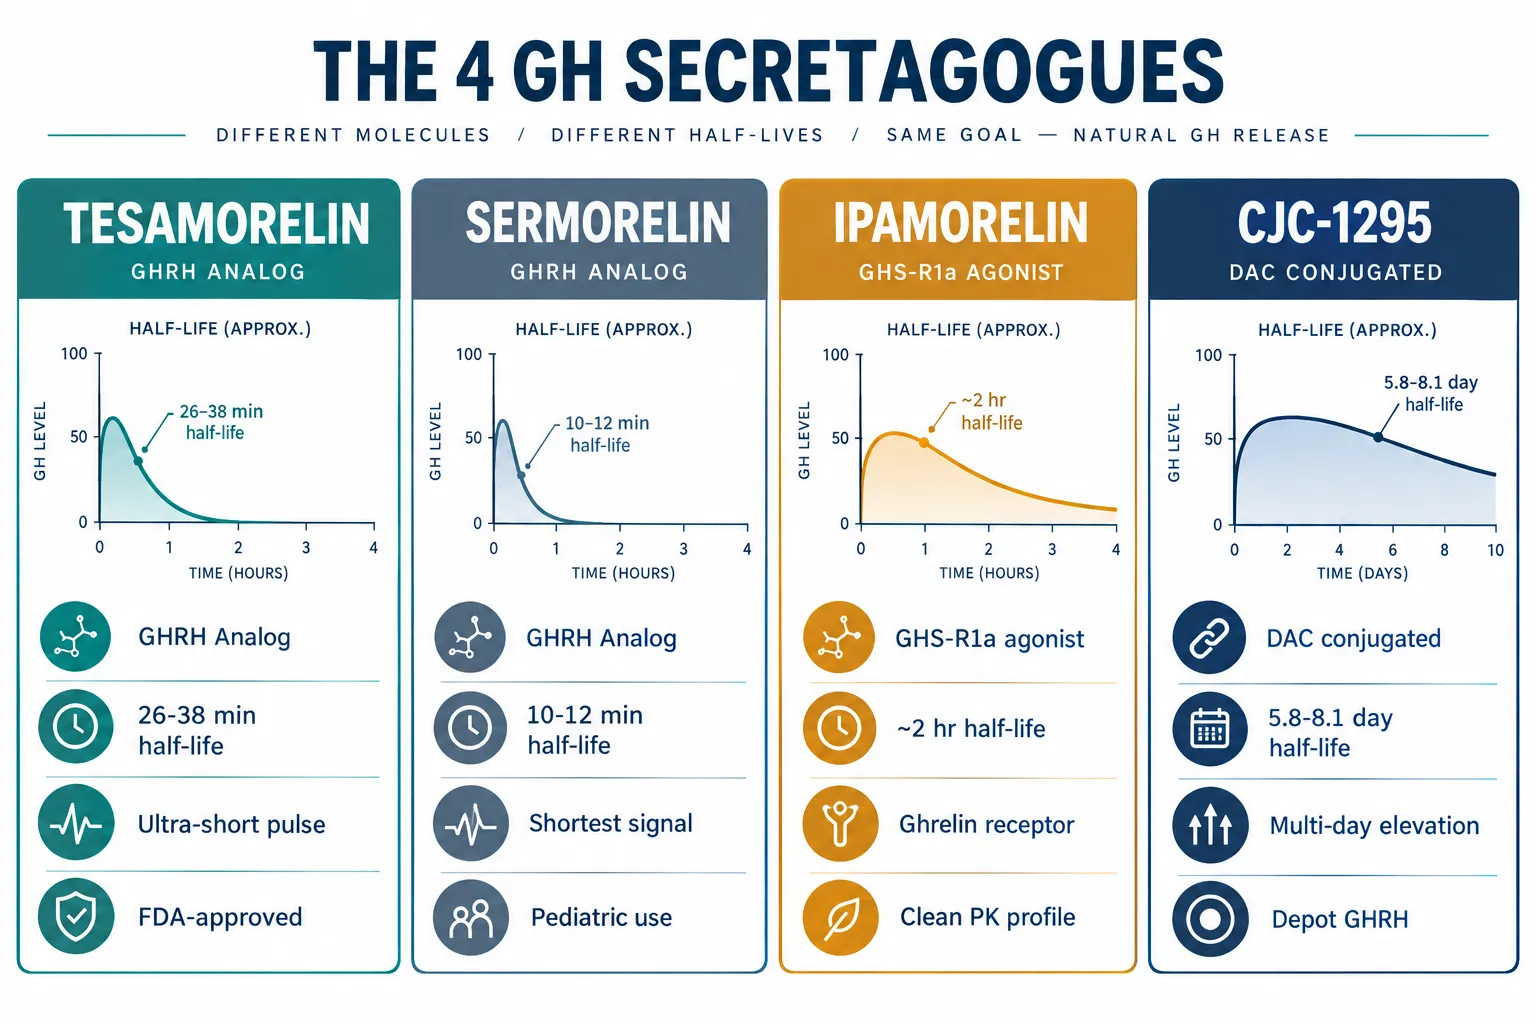
  • Tesamorelin and sermorelin are ultra-short GHRH analogs (half-lives of roughly 11-38 minutes and 10-12 minutes, respectively); assay windows must open within minutes of dosing.
  • Ipamorelin acts at a different receptor (GHS-R1a, not the GHRH receptor), carries an approximately 2-hour half-life, and generates a longer but still transient GH pulse.
  • CJC-1295 with DAC is a depot GHRH analog with a half-life of 5.8-8.1 days; it converts a single injection into a week-long endocrine signal, which fundamentally changes the experimental question.
  • DAC status is a design-level variable for CJC-1295 studies, without DAC, the half-life collapses to minutes; with DAC, it extends to days.
  • No completed human randomized trial has evaluated the CJC-1295 plus ipamorelin combination, so signal-duration synergy claims remain extrapolated from single-agent data.

Pulse Architecture: How Signal Duration Defines the Experiment

Pulse Architecture: How Signal Duration Defines the Experiment

Every GH secretagogue study is, at its foundation, a study of pulse architecture. The hypothalamic-pituitary axis releases GH in discrete bursts. Secretagogues either mimic or amplify those bursts. The key question for research design is: how long does the secretagogue's plasma signal last, and what does that mean for when you measure?

The four agents in this comparison span roughly four orders of magnitude in signal duration:

Agent Receptor Target Approximate Half-Life Signal Category
Sermorelin GHRH receptor 10-12 minutes Ultra-short
Tesamorelin GHRH receptor 11-38 minutes Ultra-short
Ipamorelin GHS-R1a (ghrelin receptor) ~2 hours Short
CJC-1295 with DAC GHRH receptor 5.8-8.1 days Long (depot)

Sermorelin is a truncated GHRH analog. Its plasma half-life of roughly 10-12 minutes means a GH pulse is triggered almost immediately after injection, and the secretagogue itself is largely cleared before most clinical blood draws are even processed. Sermorelin remains primarily used in pediatric growth hormone deficiency contexts and carries no FDA approval for adult indications, which limits the pool of controlled adult trial data.

Tesamorelin, the FDA-approved GHRH analog marketed as EGRIFTA and EGRIFTA WR, has a median time to peak plasma concentration of about 0.15 hours and a mean elimination half-life of 26-38 minutes under repeated dosing. In healthy subjects, that half-life compresses to roughly 11 minutes. Updated prescribing data for the newer EGRIFTA WR formulation confirm that reformulation did not meaningfully extend signal duration, systemic exposure (Cmax and AUC) remained comparable to the original product. For those designing studies around this agent, the science behind tesa provides useful background on its receptor-level mechanism.

"A short plasma signal does not mean a short biological effect, it means the downstream cascade, including GH secretion and IGF-1 synthesis, must be measured on a timeline that respects the signal's architecture."


Receptor-Level Intent and the Ipamorelin Distinction

Receptor-Level Intent and the Ipamorelin Distinction

One of the most consequential design errors in secretagogue research is treating ipamorelin as interchangeable with GHRH analogs. It is not. Ipamorelin activates GHS-R1a, the ghrelin receptor, not the GHRH receptor. This receptor-level distinction has direct implications for combination protocols and signal-duration comparisons.

Ipamorelin's PK profile is notably cleaner than that of older GHRPs. Its terminal half-life sits around 2 hours, clearance is approximately 0.078 L/h/kg, and its volume of distribution at steady state is about 0.22 L/kg. The dose-proportional kinetics make it a tractable agent for controlled studies. Researchers interested in sourcing this compound for preclinical work can review options under buy ipamorelin online.

Because ipamorelin works through a separate receptor, combining it with a GHRH analog is theoretically additive, each agent hits a distinct node in the GH-release pathway. However, no completed human randomized controlled trial has tested the CJC-1295 plus ipamorelin stack. Signal-duration synergy claims for this combination are extrapolated from single-agent PK/PD data, not direct combination evidence. Any research protocol treating this combination as established is building on an incomplete evidentiary foundation.

For studies using multi-agent blends, the Sermorelin Ipamorelin CJC-1295 blend page outlines how these agents are commonly combined in research contexts, while the Tesamorelin AOD9604 CJC-1295 Ipamorelin 12mg blend illustrates multi-peptide formulation approaches.


DAC Status, Assay Timing, and IGF-1 Interpretation

DAC Status, Assay Timing, and IGF-1 Interpretation

The DAC (Drug Affinity Complex) modification on CJC-1295 is not a minor formulation detail, it changes the fundamental experimental question. Without DAC, CJC-1295 behaves similarly to sermorelin: a short-acting GHRH analog cleared within minutes. With DAC, the half-life extends to 5.8-8.1 days, and a single subcutaneous injection produces GH elevations of roughly 2- to 10-fold for at least 6 days, with IGF-1 increases of approximately 1.5- to 3-fold persisting for 9-11 days.

This transforms the research design in three ways:

  1. Dosing frequency shifts from daily to weekly or biweekly.
  2. Assay timing must capture multi-day kinetics rather than a 30-60 minute post-dose window.
  3. IGF-1 as an endpoint becomes more meaningful because sustained GH elevation is required to drive meaningful IGF-1 synthesis; ultra-short agents like sermorelin or tesa generate IGF-1 changes through repeated daily pulses, not a single sustained signal.

For detailed pharmacokinetic comparisons of CJC-1295 with and without DAC, the dedicated CJC-1295 mechanism and pharmacokinetic comparison article is a primary reference.

When designing assay protocols, the following timing framework applies:

  • Sermorelin / Tesamorelin: Serum GH sampling at 15, 30, and 60 minutes post-dose; IGF-1 measured after at least 4 weeks of daily dosing.
  • Ipamorelin: Serum GH sampling at 30, 60, and 120 minutes post-dose; IGF-1 measured after sustained multi-week exposure.
  • CJC-1295 with DAC: Serum GH at 24, 48, and 96 hours post-dose; IGF-1 at days 7, 14, and 28 to capture accumulation across doses.

Misaligning assay windows with signal duration is one of the most common sources of false-negative results in secretagogue research. A study measuring GH at 4 hours post-tesa dose will miss the peak entirely.

Population PK/PD data from tesa trials in HIV-infected patients show approximately 34% higher systemic AUC compared with healthy subjects, despite similar Cmax and Tmax values. This exposure difference does not change the pulse-type time profile, it means downstream GH and IGF-1 responses may be amplified in certain populations, which must be accounted for in between-group comparisons. Researchers exploring tesa dosage parameters will find this population-level variability relevant to protocol calibration.


Conclusion

Growth-Hormone Secretagogue Research Design: Comparing Tesamorelin, CJC-1295, Ipamorelin, and Sermorelin by Signal Duration is ultimately a question of matching measurement strategy to mechanism. Each agent operates on a distinct timeline and at a distinct receptor, and treating them as interchangeable leads to flawed assay design and uninterpretable data.

Actionable next steps for researchers in 2026:

  • Classify agents by signal tier first, ultra-short (sermorelin, tesa), short (ipamorelin), or long-acting depot (CJC-1295 with DAC), before selecting endpoints or dosing intervals.
  • Confirm DAC status on any CJC-1295 source before designing a protocol; the presence or absence of DAC changes the experimental question entirely.
  • Align GH assay windows with each agent's Tmax and half-life; misaligned sampling is the most preventable source of false-negative results.
  • Treat IGF-1 as a cumulative marker, not an acute one; interpret it only in the context of dosing duration and frequency appropriate to each agent's signal length.
  • Avoid overstating combination evidence for CJC-1295 plus ipamorelin stacks until human randomized trial data are available.

Rigorous secretagogue research depends less on which peptide is chosen and more on whether the study design respects the biology of how each signal is generated, sustained, and cleared.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/growth-hormone-secretagogue-research-design-comparing-tesa-cjc-1295-ipamo.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-24 13:04:162026-09-24 13:04:16Growth-Hormone Secretagogue Research Design: Comparing Tesamorelin, CJC-1295, Ipamorelin, and Sermorelin by Signal Duration
Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts

Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts

September 20, 2026/0 Comments/in Uncategorized/by

Roughly 47% of adults in the United States carry a diagnosis of hypertension, making ACE inhibitors like lisinopril among the most prescribed drugs in modern medicine. That same cardiovascular biology sits at the center of a growing challenge in peptide research: how do labs safely study growth hormone secretagogues (GHS), compounds that measurably alter blood pressure, heart rate, and fluid balance, without losing control of their cardiovascular readouts? Understanding Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts is now a practical necessity for any team working with GHRH analogues, ghrelin mimetics, or related compounds in a controlled setting.

Key Takeaways

  • Lisinopril inhibits ACE, reducing angiotensin II production and lowering blood pressure, a mechanism directly relevant when GH secretagogues cause fluid shifts or BP changes.
  • Growth hormone secretagogues like CJC-1295, Ipamorelin, and MK-677 each carry distinct cardiovascular risk profiles that must be tracked with specific readouts.
  • MK-677 (ibutamoren) has been linked to blood pressure increases and heart failure events in long-term use, prompting FDA warning letters in late 2025.
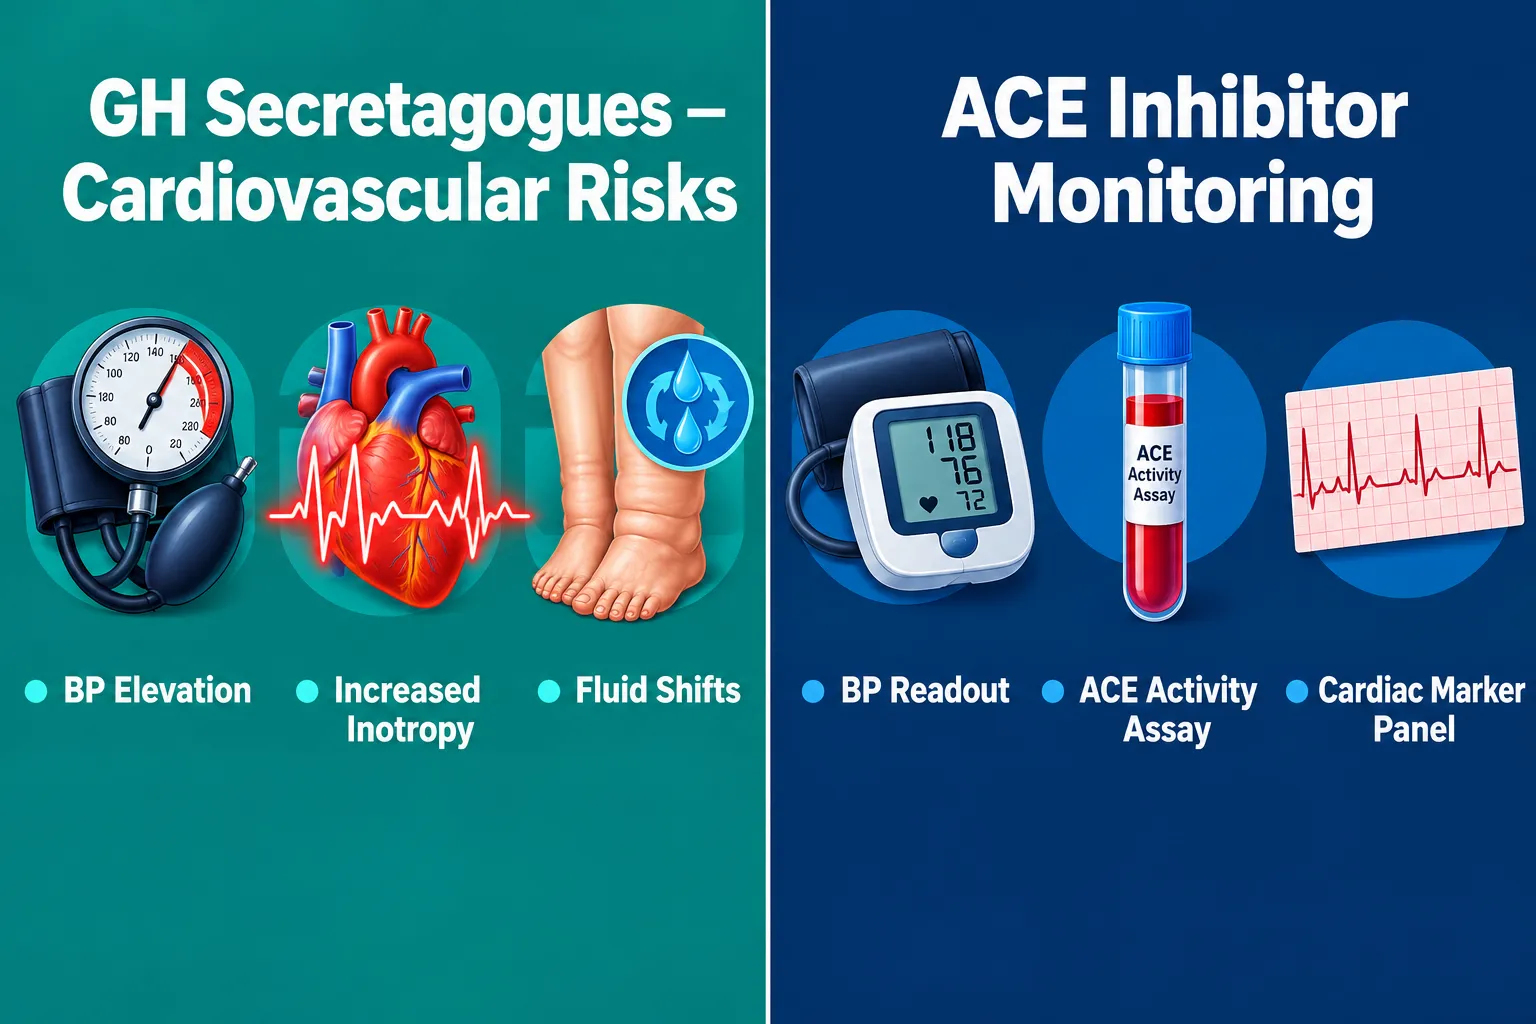
  • A structured monitoring protocol, baseline BP, ACE activity assay, serial cardiac markers, is essential before and during GHS peptide research.
  • Mitochondrial-targeted peptides such as SS-31 offer a complementary research angle with a favorable cardiovascular safety profile.

ACE Biology and Lisinopril: The Cardiovascular Foundation

ACE Biology and Lisinopril: The Cardiovascular Foundation

The renin-angiotensin-aldosterone system (RAAS) governs blood pressure, fluid volume, and electrolyte balance. At its core sits angiotensin-converting enzyme (ACE), which converts inactive angiotensin I into angiotensin II, a potent vasoconstrictor that also stimulates aldosterone release. Lisinopril binds competitively to the ACE active site, blocking this conversion and producing a cascade of cardiovascular benefits: reduced peripheral resistance, lower blood pressure, and decreased cardiac workload.

In research settings, this mechanism matters for two reasons. First, any peptide compound that independently shifts fluid balance or vascular tone will interact, directly or indirectly, with the same RAAS axis that lisinopril targets. Second, lisinopril itself accumulates bradykinin, which can cause angioedema; this safety signal must be tracked as a background variable in any multi-compound protocol.

Key ACE pathway markers to monitor in research designs:

Readout Why It Matters
Plasma ACE activity Confirms degree of enzymatic inhibition
Angiotensin II levels Tracks downstream vasoconstrictor load
Aldosterone Reflects fluid retention risk
Serum potassium Hyperkalemia risk with ACE inhibition
Bradykinin metabolites Angioedema safety signal

For researchers new to peptide biology, the Peptides 101 for Research-Use Only Buyers: Structure, Mechanisms, and resource provides a useful primer on how different compound classes interact with physiological systems.

Growth Hormone Secretagogues and Cardiovascular Risk: What the Data Show

Growth Hormone Secretagogues and Cardiovascular Risk: What the Data Show

Designing safe peptide research with cardiovascular readouts requires a clear-eyed look at how individual GHS compounds behave in the cardiovascular system. The class is not monolithic, risk profiles differ substantially across agents.

CJC-1295 and GHRH Analogues

CJC-1295 stimulates pulsatile GH release by acting on pituitary GHRH receptors. Elevated GH drives IGF-1 production, and sustained IGF-1 elevation is associated with cardiac hypertrophy and changes in left ventricular geometry in long-term animal studies. Short-term cardiovascular dynamics include modest increases in heart rate and positive inotropic effects. These changes are generally transient but require serial ECG and echocardiographic monitoring in rigorous research designs. A detailed breakdown of pharmacokinetics is available in the CJC-1295 With and Without DAC: A Detailed Mechanism and comparison guide.

Ipamorelin and Ghrelin Mimetics

Ipamorelin is a selective ghrelin receptor agonist with a cleaner selectivity profile than older GHS compounds. Ghrelin itself has demonstrated cardioprotective properties in preclinical models, improving cardiac output and reducing sympathetic tone. However, outcomes data in long-term research remain limited, and the vasodilatory effects of ghrelin-pathway activation can interact unpredictably with ACE inhibitor-induced BP lowering.

MK-677 (Ibutamoren): The Highest-Risk Profile

MK-677 presents the most significant cardiovascular concern in this class. Long-term use has been associated with measurable blood pressure increases, peripheral edema from fluid retention, and, in older research subjects, a higher incidence of heart failure events. FDA warning letters issued in December 2025 specifically flagged ibutamoren-containing products, and 2026 updates reinforced restrictions on its research use. Any protocol using MK-677 alongside an ACE inhibitor must include frequent BP monitoring and renal function panels.

"The interaction between MK-677-driven fluid retention and ACE inhibitor-mediated natriuresis creates a physiologically contested environment that demands close cardiovascular surveillance."

Designing the Protocol: Cardiovascular Readouts for Lisinopril, ACE Pathways, and Growth Hormone Secretagogues Research

Designing the Protocol: Cardiovascular Readouts for Lisinopril, ACE Pathways, and Growth Hormone Secretagogues Research

A rigorous approach to Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts starts before the first compound is introduced. The following framework reflects current best practices for preclinical and in-vitro research designs.

Step 1, Establish Cardiovascular Baseline
Record resting blood pressure, heart rate, and weight. Draw baseline panels: ACE activity, angiotensin II, aldosterone, BNP or NT-proBNP, and a complete metabolic panel. This baseline anchors all subsequent comparisons.

Step 2, Confirm ACE Inhibition Status
If lisinopril is part of the background protocol, verify plasma ACE activity is suppressed to target range before introducing any GHS compound. Residual ACE activity confounds interpretation of peptide-driven BP changes.

Step 3, Introduce GHS Compound With Staged Dosing
Begin at the lowest effective research dose. Refer to established peptide dosing frameworks for compound-specific guidance. Avoid simultaneous introduction of multiple new agents.

Step 4, Serial Cardiovascular Monitoring

  • Blood pressure: every 24-48 hours during acute phase
  • Heart rate and rhythm: ECG at baseline, 72 hours, and weekly
  • IGF-1 levels: weekly, to track GH axis activation
  • BNP/NT-proBNP: bi-weekly as a cardiac stress marker
  • Renal function and electrolytes: weekly (critical with ACE inhibitor co-administration)

Step 5, Integrate Mitochondrial Peptide Data Where Relevant
SS-31, a mitochondria-targeted antioxidant peptide, has shown cardioprotective properties in ischemia-reperfusion models without the BP or fluid-retention liabilities of GHS compounds. Researchers exploring SS-31 mitochondrial research themes may find it a useful comparator arm in cardiovascular peptide studies. Additional mechanistic background is available in the SS-31 mechanism and research overview.

Compounds to avoid combining without extensive monitoring:

  • MK-677 + lisinopril (competing fluid dynamics, hyperkalemia risk)
  • High-dose CJC-1295 + any ACE inhibitor (IGF-1-driven cardiac remodeling risk)
  • Multiple GHS agents simultaneously (additive BP and heart rate effects)

Conclusion

The intersection of lisinopril, ACE pathways, and growth hormone secretagogues is not merely pharmacological, it is a research design challenge with direct safety implications. Labs that approach this space without structured cardiovascular readouts risk misinterpreting compound effects or, worse, missing early signals of cardiac stress.

Actionable next steps for research teams:

  1. Build a standardized cardiovascular baseline panel into every GHS protocol before dosing begins.
  2. Confirm ACE inhibition status when lisinopril is a background agent, and track ACE activity throughout the study.
  3. Treat MK-677 as the highest-risk GHS compound and apply the most rigorous monitoring schedule to any protocol that includes it.
  4. Consider SS-31 as a mechanistically distinct comparator with a favorable cardiovascular profile for studies focused on cardiac or mitochondrial endpoints.
  5. Review the latest FDA guidance from late 2025 and 2026 updates on ibutamoren before finalizing any research involving that compound.

Careful protocol architecture, anchored in ACE biology and supported by serial cardiovascular readouts, is what separates rigorous peptide research from guesswork.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/lisinopril-ace-pathways-and-growth-hormone-secretagogues-designing-safe-peptide.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-20 13:06:092026-09-20 13:06:09Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts
CJC-1295 With DAC vs Without DAC: Half-Life, Release Profile, and Research Selection Guide

CJC-1295 With DAC vs Without DAC: Half-Life, Release Profile, and Research Selection Guide

September 15, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'CJC-1295 With DAC vs Without DAC' in crisp white sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge. Background: high-resolution editorial split composition showing two glass laboratory vials side by side on a clean white lab bench, one labeled DAC and one labeled No DAC, soft studio lighting with cool blue and teal tones, shallow depth of field, molecular structure silhouettes faintly visible in background, pharmaceutical research magazine cover aesthetic, professional 2-color palette of navy and teal.","content":["Annotated mechanism diagram (1536×1024) illustrating half-life extension: left panel titled 'Without DAC, Mod GRF 1-29' shows a short curved arrow labeled '30 min half-life' with callout lines pointing to 'rapid clearance', 'pulsatile GH spike', and 'enzyme degradation sites'; right panel titled 'With DAC' shows a long curved arc labeled '6-8 day half-life' with callout lines pointing to 'albumin binding site', 'sustained GH elevation', and 'DAC moiety attachment point'; clean white background, teal and navy palette, thin callout lines, editorial medical-diagram polish, landscape 1536×1024.","Four-panel labelled comparison guide (1536×1024) for GH release profiles: Panel 1 heading 'Pulsatile Release' with bullet labels 'sharp GH peak', 'mimics natural rhythm', 'short dosing window'; Panel 2 heading 'Sustained Release' with bullet labels 'blunted peak', 'prolonged elevation', 'less frequent dosing'; Panel 3 heading 'Research Use: No DAC' with bullet labels 'stack flexibility', 'timing control', 'GHRP pairing'; Panel 4 heading 'Research Use: With DAC' with bullet labels 'once-weekly dosing', 'steady baseline', 'trough monitoring'; bright clinical white background, coral and navy accent colors, thin panel dividers, editorial infographic polish, landscape format.","Numbered step-by-step research selection flow diagram (1536×1024) titled 'Selecting the Right CJC-1295 Form': Step 1 labeled 'Define Research Goal' with sub-label 'pulsatile vs steady GH'; Step 2 labeled 'Assess Dosing Frequency' with sub-label 'daily vs weekly protocol'; Step 3 labeled 'Consider Stack Partners' with sub-label 'GHRP, ipamorelin, tesa'; Step 4 labeled 'Evaluate Safety Profile' with sub-label 'tachyphylaxis risk, DAC caution'; Step 5 labeled 'Source Verified Peptide' with sub-label 'purity testing required'; connected by bold directional arrows on a clean slate-gray background, teal step nodes, white label boxes, professional research-guide aesthetic, landscape 1536×1024."]

Professional landscape hero image () with a reading "CJC-1295 With DAC vs Without DAC". CRITICAL TYPOGRAPHY RULES: render

Two peptides share nearly identical names, yet their pharmacokinetic behavior is so different that swapping one for the other in a research protocol can produce completely opposite GH release patterns. Understanding the CJC-1295 with DAC vs without DAC distinction, including half-life, release profile, and research selection, is one of the most practically important decisions in growth hormone secretagogue research today.

Key Takeaways

  • CJC-1295 without DAC (also called Mod GRF 1-29) has a half-life of roughly 30 minutes, producing a sharp, pulsatile GH spike.
  • CJC-1295 with DAC binds to albumin in plasma, extending its half-life to approximately 6-8 days and producing a sustained, blunted GH elevation.
  • The two variants are not interchangeable; each suits different research designs and stacking strategies.
  • Nomenclature confusion is common, "CJC-1295 no DAC" and "Mod GRF 1-29" refer to the same peptide.
  • Both remain research-only compounds in 2026, with no approved clinical indications.

What Is CJC-1295 and Why Does DAC Change Everything

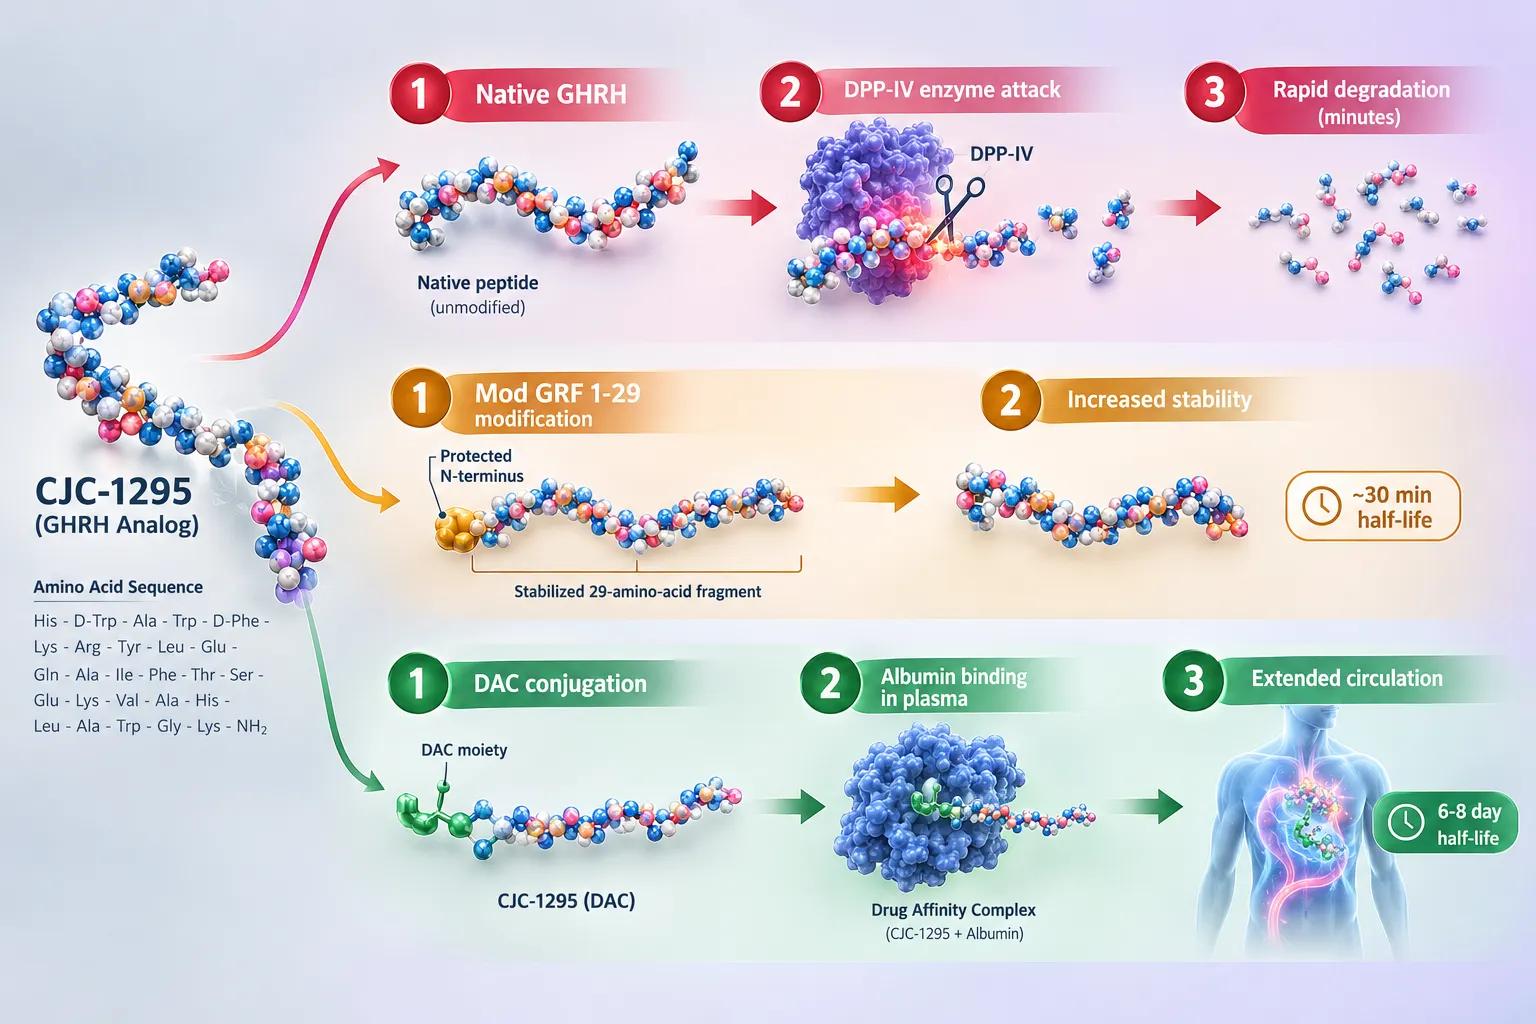
CJC-1295 is a synthetic analogue of growth hormone-releasing hormone (GHRH). Native GHRH is rapidly degraded by dipeptidyl peptidase IV (DPP-IV) enzymes in plasma, giving it a half-life of only a few minutes. Early modifications produced Mod GRF 1-29, a stabilized 29-amino-acid fragment with a half-life extended to roughly 30 minutes. This version is widely sold as "CJC-1295 without DAC" or simply "CJC-1295 no DAC."

The Drug Affinity Complex (DAC) technology takes stabilization a step further. A lysine residue is modified with a maleimidoproprionic acid group that forms a covalent bond with circulating albumin. Because albumin itself has a half-life of roughly 19 days, the DAC-conjugated peptide is shielded from clearance, extending its effective half-life to approximately 6-8 days in research models.

For a deeper look at the structural and pharmacokinetic differences between these two forms, the CJC-1295 with and without DAC mechanism and pharmacokinetic comparison covers the underlying science in detail.

What Is CJC-1295 and Why Does DAC Change Everything

The core structural difference:

Feature Mod GRF 1-29 (No DAC) CJC-1295 With DAC
Half-life ~30 minutes ~6-8 days
Albumin binding No Yes (covalent)
GH release pattern Pulsatile spike Sustained elevation
Dosing frequency Daily or per-session Once or twice weekly
DPP-IV resistance Partial High

Release Profile: Pulsatile vs Sustained GH Stimulation

The half-life gap between these two variants directly determines their GH release profiles, and this distinction sits at the heart of the CJC-1295 with DAC vs without DAC research selection guide.

Mod GRF 1-29 (no DAC) produces a sharp, high-amplitude GH pulse that mirrors the body's natural episodic secretion pattern. Peak GH levels appear within 15-30 minutes of administration and return to baseline within a few hours. This pulsatile pattern is considered physiologically favorable by many researchers because it preserves the natural on-off rhythm of the somatotropic axis. It also offers precise timing control, making it easier to pair with ghrelin mimetics like ipamorelin or GHRP-2 for synergistic GH release.

Researchers studying GH secretagogue stacks often combine Mod GRF 1-29 with ipamorelin, as explored in resources on sermorelin, ipamorelin, and CJC-1295 combination protocols.

CJC-1295 with DAC produces a blunted but prolonged GH elevation. The Teichman 2006 Phase 1 study remains the most-cited pharmacokinetic anchor for this variant, demonstrating dose-dependent increases in IGF-1 lasting several days after a single injection. This sustained profile reduces the need for daily dosing but also raises concerns about tachyphylaxis, a desensitization of pituitary receptors caused by continuous GHRH stimulation rather than intermittent pulses.

"A sustained GH elevation is not automatically superior to a pulsatile one. The research question determines which profile is appropriate."

Release Profile: Pulsatile vs Sustained GH Stimulation

Researchers interested in body composition outcomes, including visceral fat reduction, may find relevant context in visceral fat research protocols that examine GH secretagogue effects on adipose tissue.

Research Selection Guide: Choosing Between CJC-1295 With DAC vs Without DAC

Selecting the correct variant depends on three primary research variables: the desired GH release pattern, the dosing schedule, and the peptide stack being used.

Choose Mod GRF 1-29 (no DAC) when:

  • The protocol requires mimicking natural pulsatile GH secretion
  • Daily or per-session administration is feasible
  • The peptide will be stacked with a GHRP or ipamorelin for amplified pulse height
  • Researchers want fine-grained control over timing and amplitude

Choose CJC-1295 with DAC when:

  • The protocol benefits from less frequent dosing (once or twice weekly)
  • A sustained IGF-1 elevation is the primary endpoint
  • The research design does not require precise pulse timing
  • Stacking with other secretagogues is not a primary concern

For multi-peptide research designs, blended formulations such as tesa, CJC-1295, and ipamorelin combination protocols offer an alternative approach worth reviewing.

Researchers should also note that the DAC variant carries a more cautious safety profile in 2026 consensus literature. Continuous GHRH receptor stimulation raises questions about receptor downregulation, and some protocols now include structured off-weeks when using the DAC form. The no-DAC variant's short half-life makes receptor rest automatic between doses.

For context on how other peptide classes interact with endocrine pathways, the overview of peptides and polypeptides in endocrine pharmacology provides useful background on receptor biology.

Research Selection Guide: Choosing Between CJC-1295 With DAC vs Without DAC

Nomenclature note: The label "CJC-1295 no DAC" is a vendor convention, not an official chemical name. The correct scientific designation is Modified GRF 1-29 (Mod GRF 1-29). Researchers sourcing peptides should confirm which compound is actually present, as mislabeling remains a documented issue in the research peptide supply chain.

Both compounds remain strictly research-use-only substances in 2026 with no approved human therapeutic applications.

Conclusion

The CJC-1295 with DAC vs without DAC comparison is not a question of which peptide is better, it is a question of which release profile matches the research objective. Mod GRF 1-29 delivers a short, sharp GH pulse ideal for pulsatile protocols and multi-peptide stacks. CJC-1295 with DAC delivers sustained GH elevation suited to low-frequency dosing designs, but demands greater attention to receptor desensitization risk.

Actionable next steps for researchers in 2026:

  1. Confirm the exact compound identity before designing any protocol, verify whether the supplier is providing Mod GRF 1-29 or the DAC-conjugated form.
  2. Match the release profile to the research endpoint: pulsatile for physiological mimicry, sustained for steady IGF-1 elevation studies.
  3. Review stacking compatibility before combining either variant with GHRPs or other secretagogues.
  4. Source only from suppliers with documented third-party purity testing to ensure compound integrity.
  5. Monitor current literature, as mid-2026 consensus continues to favor the no-DAC variant for most stacked research designs due to its more controllable pharmacokinetic profile.
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cjc-1295-with-dac-vs-without-dac-half-life-release-profile-and-research-selectio.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-15 13:05:092026-09-15 13:05:09CJC-1295 With DAC vs Without DAC: Half-Life, Release Profile, and Research Selection Guide
Best Research‑Use GH Secretagogue Peptides: Comparing CJC‑1295 (With and Without DAC), Ipamorelin, and Tesamorelin

Best Research‑Use GH Secretagogue Peptides: Comparing CJC‑1295 (With and Without DAC), Ipamorelin, and Tesamorelin

September 2, 2026/0 Comments/in Uncategorized/by

Growth hormone secretagogue research has expanded sharply since 2020, yet fewer than one in four investigators working with these compounds can clearly articulate why half-life differences between CJC-1295 variants change their assay endpoints. Choosing the wrong peptide for a given experimental design wastes reagents, distorts GH pulse data, and undermines reproducibility. This buyer's guide for research labs breaks down the Best Research-Use GH Secretagogue Peptides: Comparing CJC-1295 (With and Without DAC), Ipamorelin, and Tesamorelin across the variables that matter most: mechanism, pharmacokinetics, regulatory standing, and fit for specific study designs.

Key Takeaways

  • CJC-1295 with DAC provides a prolonged, near-continuous GH elevation useful for chronic exposure models; without DAC it mimics natural pulsatile release.
  • Ipamorelin is the most selective ghrelin-receptor agonist in this class, making it valuable for mechanistic studies that need to isolate GHS-R1a signaling.
  • Tesamorelin is the only FDA-approved compound in this group, with the strongest clinical evidence base and a recently updated formulation (EGRIFTA WR).
  • For multi-peptide stack research, synergistic GHRH-plus-GHSR designs can amplify GH output beyond what either compound achieves alone.
  • Regulatory and anti-doping status differs sharply across these peptides and must be factored into any research protocol or sourcing decision.

Understanding the Pharmacological Landscape of GH Secretagogue Peptides

Understanding the Pharmacological Landscape of GH Secretagogue Peptides

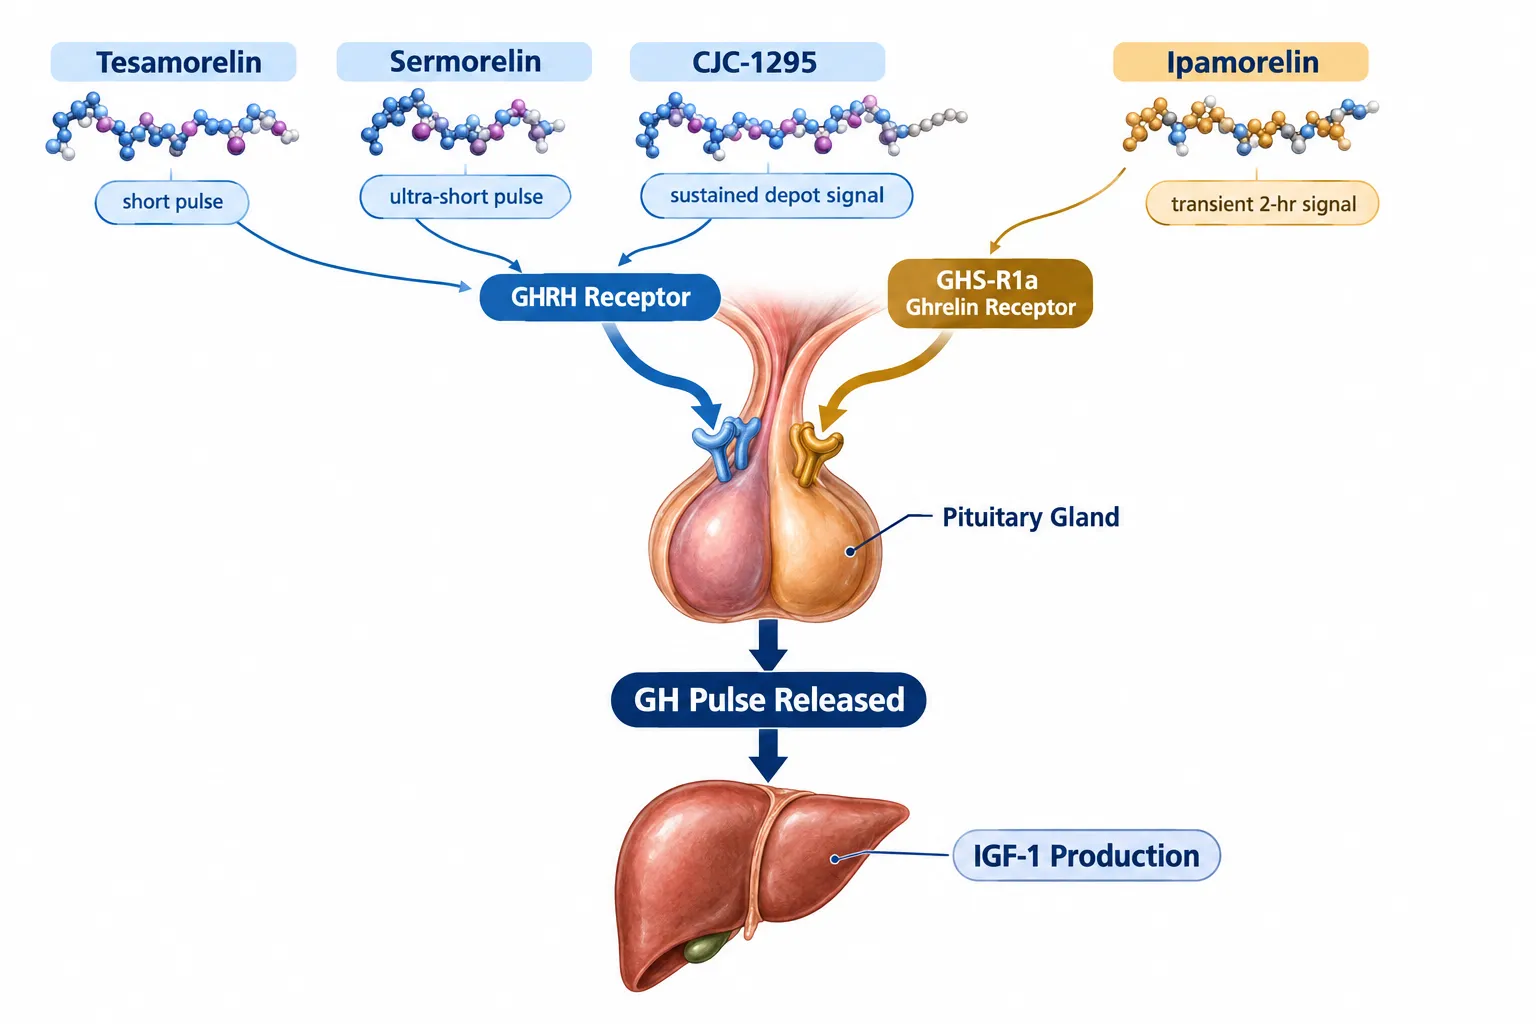
The Best Research-Use GH Secretagogue Peptides: Comparing CJC-1295 (With and Without DAC), Ipamorelin, and Tesamorelin all stimulate GH release, but they do so through distinct receptor pathways. CJC-1295 and tesa act at the GHRH receptor on pituitary somatotrophs. Ipamorelin acts at the GHS-R1a (ghrelin) receptor. This distinction is not trivial for experimental design.

GHRH-receptor agonists (CJC-1295 variants, tesa) amplify the amplitude of GH pulses. GHS-R1a agonists (ipamorelin) primarily increase pulse frequency and can act synergistically when combined with GHRH-pathway compounds. Researchers designing assays around IGF-1 AUC, pulse frequency, or receptor-specific downstream signaling need to select accordingly.

CJC-1295 With DAC vs. Without DAC: A Critical Distinction

The Drug Affinity Complex (DAC) modification covalently binds CJC-1295 to circulating albumin, extending its half-life from roughly 30 minutes to approximately 8 days. The practical consequences for research are significant:

Parameter CJC-1295 Without DAC CJC-1295 With DAC
Half-life ~30 minutes ~6-8 days
GH release pattern Pulsatile (physiological) Sustained, blunted pulsatility
Best assay fit Pulse-frequency studies Chronic GH-exposure models
Dosing frequency Multiple daily Once or twice weekly

CJC-1295 without DAC is the better tool when pulsatility itself is the endpoint. It produces a sharp, short GH spike that mirrors endogenous GHRH-driven release. CJC-1295 with DAC suits chronic body-composition or metabolic models where sustained GH elevation, rather than pulse architecture, is the variable of interest. Neither compound has cleared phase III clinical trials, and both remain unapproved. They are also banned under the World Anti-Doping Agency code, a factor relevant to any research that interfaces with sport science. For labs exploring combination approaches, the Sermorelin Ipamorelin CJC-1295 dosage resource offers useful context on multi-peptide protocol considerations.

Ipamorelin: Selectivity as a Research Advantage

Ipamorelin: Selectivity as a Research Advantage

Among all GHS-R1a agonists studied in humans, ipamorelin stands out for its receptor selectivity. Unlike earlier ghrelin mimetics such as GHRP-6, ipamorelin does not meaningfully elevate cortisol, prolactin, or ACTH at research-relevant doses. This makes it a cleaner tool for isolating GH-axis effects without confounding hormonal noise.

Human safety data, while limited in volume, show a generally benign profile. The compound has not produced serious adverse signals in short-term studies. However, ipamorelin's clinical development effectively stalled after a pivotal efficacy trial failed to meet its primary endpoint, and no regulatory approval has followed. Compounding scrutiny of ipamorelin has also increased between 2024 and 2026, narrowing its availability through pharmacy channels.

For research purposes, ipamorelin's value is clearest in two scenarios:

  • Mechanistic GHS-R1a studies where receptor-specific signaling must be isolated
  • Stack designs pairing ipamorelin with a GHRH-pathway compound to achieve synergistic GH output

The CJC-1295 IPA 10mg combination format reflects this stack logic. Labs interested in broader systemic peptide research contexts can also review the systemic peptide research resource library for supporting literature.

Tesamorelin: The Gold Standard for Evidence-Based GH Secretagogue Research

Tesamorelin: The Gold Standard for Evidence-Based GH Secretagogue Research

Tesamorelin occupies a different tier entirely. It is a stabilized synthetic analog of endogenous GHRH and the only compound in this comparison with FDA approval. Originally cleared for HIV-associated lipodystrophy, its label was revised in 2025-2026 to reflect the new EGRIFTA WR (F8) formulation, which offers improved stability and reconstitution characteristics relevant to both clinical and research settings.

The evidence base for tesa is substantially deeper than for either CJC-1295 variant or ipamorelin. Randomized controlled trial data confirm meaningful reductions in visceral adipose tissue in people with HIV-associated lipodystrophy. More recently, tesa has shown the strongest disease-modifying signals of any compound in this class for non-alcoholic fatty liver disease (NAFLD) in HIV-positive populations, a finding that has driven an active 2026 research pipeline focused on NAFLD extension and body-composition outcomes.

Researchers benefit from tesa's approval status in several ways:

  • Published pharmacokinetic and safety data are extensive and peer-reviewed
  • Regulatory-grade sourcing is available through licensed channels
  • The compound can serve as a positive control in GH-secretagogue assay panels

For labs designing fat-metabolism or metabolic-syndrome models, reviewing the tesa benefits and tesa dosage for fat loss literature provides a strong foundation. Labs examining safety profiles should also consult the tesa side effects data before designing protocols. For those evaluating tesa against other GHRH-class compounds, the tesa vs. sermorelin comparison is a useful reference point.

Choosing the Right Peptide or Stack for Your Experimental Design

The decision framework below summarizes how to match compound to research objective:

Use CJC-1295 without DAC when: the study endpoint is GH pulse frequency, amplitude, or pulsatility architecture under acute stimulation conditions.

Use CJC-1295 with DAC when: the model requires sustained GH elevation over days or weeks without repeated dosing, such as chronic metabolic or tissue-remodeling studies.

Use ipamorelin when: the research question isolates GHS-R1a signaling, or when a clean GH stimulus is needed without cortisol or prolactin interference. Combining ipamorelin with a GHRH-pathway peptide amplifies GH output through complementary receptor mechanisms.

Use tesa when: the study requires an FDA-approved reference compound, when visceral adiposity or NAFLD endpoints are primary, or when the research must align with published clinical benchmarks. Multi-peptide blend formats such as the Tesamorelin CJC-1295 Ipamorelin 12mg blend are available for labs exploring combined-pathway designs.

Conclusion

Selecting among the Best Research-Use GH Secretagogue Peptides: Comparing CJC-1295 (With and Without DAC), Ipamorelin, and Tesamorelin is fundamentally an experimental-design decision, not a preference. CJC-1295 without DAC is the tool for pulsatility research; CJC-1295 with DAC suits chronic-exposure models; ipamorelin delivers receptor selectivity for mechanistic work; and tesa provides the only clinically validated, regulatory-grade option in the group.

Actionable next steps for research teams:

  1. Define the primary assay endpoint first (pulse architecture, IGF-1 AUC, body composition, receptor signaling) before selecting a compound.
  2. Review the current regulatory and anti-doping status of any unapproved compound before sourcing or publishing.
  3. Consider tesa as a positive control in any GH-secretagogue panel to anchor results to published clinical benchmarks.
  4. For stack designs, pair a GHRH-pathway compound with ipamorelin to exploit complementary receptor mechanisms and maximize GH output in the model.
  5. Source from suppliers that provide third-party purity testing documentation to ensure assay reproducibility.
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/best-research-use-gh-secretagogue-peptides-comparing-cjc-1295-with-and-without-d.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-02 13:04:272026-09-02 13:04:27Best Research‑Use GH Secretagogue Peptides: Comparing CJC‑1295 (With and Without DAC), Ipamorelin, and Tesamorelin
CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show

September 2, 2026/0 Comments/in Uncategorized/by

Growth hormone secretagogue research has quietly shifted gears. Where earlier studies focused almost exclusively on peak GH output, the conversation around CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show has expanded to include tissue recovery timelines, glucose-handling endpoints, and combination stacking strategies that were barely discussed five years ago. Researchers and clinicians in 2026 are asking more nuanced questions, not just "does IGF-1 rise?" but "what does that rise actually do in a metabolic or recovery context?"

Key Takeaways

  • CJC‑1295 with DAC offers a prolonged half-life suited to weekly dosing, while the no-DAC form aligns better with circadian-timed, daily micro-dose protocols.
  • Stacking CJC‑1295 with ipamorelin has become the dominant 2026 protocol pattern in both clinical and research settings.
  • IGF-1 elevation is well-documented, but hard endpoints for recovery and body composition remain limited in the published evidence base.
  • Desensitization risk with the DAC form makes structured washout periods a standard protocol feature in 2026 monographs.
  • Combination protocols now extend to Tesamorelin and metabolic peptides, broadening the research scope beyond classic GH modeling.

Understanding the Two Forms: DAC vs. No-DAC

Understanding the Two Forms: DAC vs. No-DAC

The core structural difference between the two variants drives nearly every protocol decision. CJC‑1295 with DAC (Drug Affinity Complex) binds to albumin in the bloodstream, dramatically extending its half-life to approximately eight days. This makes once-weekly or twice-monthly dosing pharmacologically feasible and reduces injection burden in longer research cycles.

CJC‑1295 without DAC, sometimes called Modified GRF(1-29), has a half-life of roughly 30 minutes. That short window is not a disadvantage in every context. Researchers exploring circadian-aligned dosing argue that brief, timed pulses more closely mimic the body's natural growth hormone release patterns, particularly when administered before sleep or around training windows.

Key pharmacokinetic comparison:

Feature With DAC Without DAC
Half-life ~8 days ~30 minutes
Dosing frequency Weekly or bi-weekly Daily or twice daily
GH pulse pattern Sustained elevation Acute, pulsatile
Desensitization risk Higher Lower
Protocol washout need Yes, structured Minimal

Desensitization is a genuine concern with the DAC form. Prolonged receptor stimulation can blunt pituitary responsiveness over time. Current somatotropin research protocols in 2026 address this by building in four-to-six-week washout periods after eight-to-twelve-week active cycles.

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show About Combination Stacking

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show About Com

The most significant protocol shift in 2026 is the near-universal pairing of CJC‑1295 with ipamorelin. Ipamorelin is a selective ghrelin receptor agonist that stimulates GH release through a complementary pathway. Together, the two peptides produce a synergistic GH pulse without the cortisol or prolactin elevation associated with older secretagogues.

"The combination of a GHRH analog with a selective ghrelin mimetic has become the reference stack in 2026 protocol literature, it amplifies the GH signal while keeping the hormonal side-effect profile narrow."

For researchers interested in this pairing, resources on sermorelin, ipamorelin, and CJC-1295 dosing provide useful context on how dosing ratios are being structured. A related product reference for lab-grade material is the CJC-1295 IPA 10mg formulation used in current research settings.

Beyond ipamorelin, 2026 protocols are increasingly incorporating Tesamorelin, an FDA-approved GHRH analog with a documented record from HIV lipodystrophy trials. That clinical history provides safety signals that pure research peptides lack. Researchers exploring this avenue can review the Tesamorelin and CJC-1295 combination framework, which positions both analogs within the broader GHRH class. Multi-peptide blends, such as those covered in Tesamorelin, CJC-1295, and ipamorelin 12mg blend protocols, are also appearing in emerging metabolic research designs.

Common 2026 stacking configurations:

  • CJC‑1295 (no DAC) + ipamorelin: nightly, circadian-timed
  • CJC‑1295 (with DAC) + ipamorelin: weekly CJC, daily ipamorelin
  • CJC‑1295 + Tesamorelin + ipamorelin: multi-target metabolic protocols
  • CJC‑1295 + AOD-9604 blends: body composition-focused research designs

What the Evidence Actually Shows, and Where It Falls Short

What the Evidence Actually Shows, and Where It Falls Short

Honest assessment of the evidence base matters here. IGF-1 elevation following CJC‑1295 administration is consistently documented across multiple study designs. That finding is robust. What remains less clear is the translation of that IGF-1 rise into hard clinical endpoints.

What is reasonably supported:

  • Dose-dependent increases in IGF-1 and GH
  • Improved lean mass markers in some body composition studies
  • Potential benefits in tissue recovery research contexts, particularly around collagen synthesis pathways
  • Modest improvements in sleep quality linked to nocturnal GH pulsatility

What remains speculative or under-studied:

  • Long-term glucose metabolism effects at fixed clinic doses vs. weight-based trial doses
  • Durability of body composition changes after cycle cessation
  • Comparative efficacy of DAC vs. no-DAC forms on recovery-specific endpoints
  • Safety profile in populations beyond healthy adults and HIV lipodystrophy patients

The gap between weight-based dosing used in clinical trials and the fixed doses common in clinic or biohacking settings is a persistent methodological problem. Most trial data comes from weight-adjusted protocols; most real-world use does not follow that model. Researchers tracking tissue repair research outcomes need to account for this discrepancy when interpreting results.

Lab-based monitoring, specifically IGF-1, fasting glucose, and HbA1c panels, is now considered standard practice in responsible 2026 protocol designs, particularly for cycles exceeding eight weeks.

Conclusion

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show points toward a maturing field that is moving beyond simple GH elevation as a goal. The DAC form suits sustained, low-frequency dosing with structured washout; the no-DAC form fits circadian-aligned, pulsatile strategies. Combination stacking with ipamorelin and Tesamorelin is now the research norm rather than the exception.

Actionable next steps for researchers and clinicians:

  1. Select the CJC‑1295 variant based on dosing frequency needs and desensitization tolerance, not convenience alone.
  2. Pair with ipamorelin for synergistic GH pulse amplification with a cleaner hormonal side-effect profile.
  3. Establish baseline IGF-1, fasting glucose, and HbA1c before any cycle begins.
  4. Build washout periods into DAC-based protocols, typically four to six weeks after an eight-to-twelve-week active phase.
  5. Interpret body composition and recovery outcomes against trial-dosing literature with appropriate caution given the fixed-dose gap.

The evidence base will sharpen as more combination protocols generate structured outcome data. Until then, disciplined lab monitoring and conservative cycle design remain the most defensible approach.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cjc-1295-with-and-without-dac-in-emerging-recovery-and-metabolic-research-what-2-1.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-02 13:04:042026-09-02 13:04:04CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show
Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides

Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides

September 1, 2026/0 Comments/in Uncategorized/by

Men with obesity-related secondary hypogonadism can show testosterone levels up to 30% lower than age-matched lean controls, yet the endocrine axis disruption extends far beyond a single hormone. Understanding estrogen receptors, enclomiphene, and peptide hormones: how serms interface with GLP-class and growth hormone peptides is now central to advanced endocrine research protocols that model multiple hormonal axes simultaneously. As GLP-1 receptor agonists and GHRH analogues become fixtures in metabolic and body-composition research, the question of how a selective estrogen receptor modulator like enclomiphene fits into those multi-peptide frameworks has become increasingly important.

Key Takeaways

  • Enclomiphene blocks hypothalamic estrogen receptors to raise LH, FSH, and endogenous testosterone without suppressing spermatogenesis.
  • Systematic evidence shows serms can increase total testosterone by a mean of roughly 274 ng/dL versus placebo in functional hypogonadism.
  • GLP-class peptides such as Retatrutide and GLP-2-T act on gut-brain and metabolic axes that indirectly influence sex hormone binding and HPG axis tone.
  • GHRH analogues like CJC-1295 amplify growth hormone pulses and raise IGF-1, creating a separate but intersecting endocrine signal relevant to serm protocols.
  • Formal combination trials of enclomiphene with GLP-class or GHRH peptides remain an open research frontier as of 2026.

How Enclomiphene Modulates Estrogen Receptors in the HPG Axis

Enclomiphene is the trans-isomer of clomiphene. Unlike its cis-isomer zuclomiphene, it acts as a clean antagonist at hypothalamic estrogen receptors, blocking the negative feedback signal that estrogen normally sends to suppress gonadotropin-releasing hormone. The result is a coordinated rise in luteinizing hormone (LH) and follicle-stimulating hormone (FSH), which in turn drives endogenous testicular testosterone production.

How Enclomiphene Modulates Estrogen Receptors in the HPG Axis

This mechanism distinguishes enclomiphene sharply from exogenous testosterone replacement. Testosterone replacement shuts down the HPG axis through negative feedback; enclomiphene does the opposite. A systematic review and meta-analysis of ten randomized controlled trials covering 819 men found that serm therapy, primarily clomiphene and enclomiphene, raised total testosterone by a mean of approximately 274 ng/dL compared with placebo, while sperm parameters remained intact.

A 2026 British Society for Sexual Medicine position statement reinforces this picture. In one referenced RCT of 44 men, daily enclomiphene was non-inferior to transdermal testosterone at both 24 hours and 6 weeks. A retrospective series of 66 men showed a median testosterone increase of 5.76 nmol/L after roughly 9 months of therapy. For researchers exploring serm therapy protocols, these figures establish a meaningful hormonal baseline.

Why metabolic context matters: Men with obesity, type 2 diabetes, or metabolic syndrome often present with reversible hypothalamic-pituitary dysfunction, a profile where enclomiphene's upstream mechanism is particularly well-matched. Elevated aromatase activity in adipose tissue converts more testosterone to estradiol, deepening the hypothalamic feedback suppression that enclomiphene is designed to interrupt.

"Enclomiphene's value lies not just in raising testosterone, but in preserving the entire upstream signaling architecture, a distinction that matters enormously when modeling multi-axis endocrine protocols."

GLP-Class Peptides and Their Indirect Influence on Estrogen Receptor Signaling

The GLP-class of peptides, including GLP-1 receptor agonists, the dual/triple agonist Retatrutide (GLP-1/GIP/glucagon), and GLP-2-T analogues, operate primarily on gut-brain signaling, insulin secretion, and energy homeostasis. Their connection to estrogen receptor biology is indirect but mechanistically significant.

GLP-Class Peptides and Their Indirect Influence on Estrogen Receptor Signaling

GLP-1 receptor agonists reduce adipose mass. Because adipose tissue is the primary peripheral site of aromatase-driven estrogen synthesis in men, a meaningful reduction in fat mass lowers circulating estradiol. Lower estradiol reduces the hypothalamic estrogen receptor load that enclomiphene must overcome. In practical terms, a subject on a GLP-class agent may show a more responsive HPG axis to serm intervention.

Retatrutide, as a triple agonist targeting GLP-1, GIP, and glucagon receptors, produces more pronounced body-composition shifts than single-agonist agents. Research on tirzepatide peptide, a dual GLP-1/GIP agonist with a related mechanism, illustrates how GLP-class compounds can reshape the metabolic environment in which hormonal axes operate.

GLP-2-T analogues primarily target intestinal epithelial GLP-2 receptors, influencing gut integrity and nutrient absorption. Their relevance to estrogen receptor cross-talk is more distal but may include effects on enterohepatic estrogen recirculation, a pathway that modulates systemic estradiol levels and, consequently, hypothalamic feedback tone.

Researchers working with single peptide protocols often note that isolating one axis at a time provides cleaner data before combining agents, a principle that applies directly to serm-plus-GLP-class study design.

GHRH Analogues, Growth Hormone Peptides, and serm Protocol Integration

CJC-1295 is a synthetic GHRH analogue that extends the half-life of endogenous GHRH, amplifying pulsatile growth hormone release from the anterior pituitary and raising downstream IGF-1 levels. This creates a third endocrine axis, the GH/IGF-1 axis, that intersects with both the HPG axis and the metabolic effects of GLP-class peptides.

GHRH Analogues, Growth Hormone Peptides, and serm Protocol Integration

The relevance to estrogen receptor biology is bidirectional. IGF-1 has been shown to modulate estrogen receptor expression in multiple tissue types. Elevated GH and IGF-1 also influence body composition, reducing fat mass and increasing lean tissue, which feeds back into aromatase activity and circulating estradiol, the same variable that enclomiphene targets at the receptor level.

For researchers modeling endocrine axes, the interaction matrix looks like this:

Agent Primary Target Indirect Effect on ER Signaling
Enclomiphene Hypothalamic ER Direct blockade, raises LH/FSH
GLP-1/Retatrutide GLP-1/GIP/Glucagon R Reduces adipose aromatase substrate
CJC-1295 GHRH receptor IGF-1 modulates ER expression; body comp shift
GLP-2-T Intestinal GLP-2 R Enterohepatic estrogen recirculation effects

Researchers exploring serms in combination with growth hormone peptides should account for these intersecting signals when designing outcome measures. Sports peptides research has long recognized that GH-axis and sex-hormone-axis interventions produce non-additive effects, a principle that extends to serm-plus-GHRH analogue modeling.

Enclomiphene's clinical profile also makes it suitable for populations where erythrocytosis risk from testosterone replacement is a concern, a relevant consideration when subjects are simultaneously on GH-stimulating peptides that affect red blood cell precursor signaling.

As of 2026, formal combination trials pairing enclomiphene with GLP-class agents or GHRH analogues have not been published. This represents a significant gap in the literature and a clear frontier for structured research protocols.

Conclusion

The intersection of estrogen receptors, enclomiphene, and peptide hormones, how serms interface with GLP-class and growth hormone peptides, is one of the most mechanistically rich areas in current endocrine research. Enclomiphene provides a targeted, fertility-preserving tool for HPG axis restoration. GLP-class peptides reshape the metabolic environment that determines how much estrogenic feedback the hypothalamus receives. GHRH analogues like CJC-1295 add a third dimension through IGF-1-mediated effects on receptor expression and body composition.

Actionable next steps for researchers and clinicians:

  • Map baseline estradiol, LH, FSH, and testosterone before introducing any multi-agent protocol.
  • Consider GLP-class-driven fat-mass reduction as a preparatory phase that may enhance enclomiphene responsiveness.
  • Use validated assays for both total and free testosterone, IGF-1, and estradiol when modeling combined serm-plus-peptide protocols.
  • Monitor spermatogenesis parameters if fertility preservation is a stated research or clinical objective.
  • Prioritize single-axis baseline data before combining enclomiphene with GHRH analogues to isolate each variable's contribution.

The endocrine axes do not operate in isolation. Research protocols that treat them as interconnected systems, rather than independent targets, will generate the most meaningful data as this field matures.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/estrogen-receptors-enclomiphene-and-peptide-hormones-how-serms-interface-with-gl.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-01 13:05:082026-09-01 13:05:08Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides
CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models

CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models

August 29, 2026/0 Comments/in Uncategorized/by

Fewer than a dozen peer-reviewed human trials have examined CJC‑1295 in any form since its synthesis, yet community dosing protocols for metabolic optimization and injury recovery have multiplied rapidly. That gap between widespread use and thin clinical evidence is exactly what makes CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models one of the most pressing topics in peptide science heading into 2026.

Key Takeaways

  • CJC‑1295 with DAC has a confirmed extended half-life of roughly six to eight days; the without-DAC variant acts in minutes and is largely uncharacterized in peer-reviewed human literature.
  • Growth hormone and IGF‑1 response data exist primarily for the DAC form; metabolic, body-composition, and recovery outcomes remain evidence gaps for both variants.
  • Community dosing for recovery and metabolism is protocol-driven, not evidence-driven, creating meaningful safety unknowns.
  • Stacking CJC‑1295 with Tesamorelin or Ipamorelin is a growing research model, but formal combination trial data are absent.
  • Regulatory and compounding restrictions tightened between 2023 and 2026, making purity verification a critical step for any research application.

The Pharmacokinetic Foundation: DAC vs. Without DAC

The Pharmacokinetic Foundation: DAC vs. Without DAC

Understanding CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models begins with the chemistry that separates the two variants.

CJC‑1295 with DAC incorporates a Drug Affinity Complex, a chemical modification that allows the peptide to bind reversibly to serum albumin. This binding dramatically extends its half-life to approximately six to eight days, producing a sustained elevation of growth hormone-releasing hormone (GHRH) activity. The result is a prolonged, blunted GH pulse that differs significantly from the body's natural pulsatile secretion pattern.

CJC‑1295 without DAC (sometimes called Modified GRF 1-29 or Mod GRF) lacks that albumin-binding modification. Its half-life is roughly 30 minutes, making it far more aligned with physiologic GHRH signaling. This shorter window is precisely why researchers and practitioners pair it with a GHRP such as Ipamorelin, to amplify a single, timed GH pulse.

Feature With DAC Without DAC
Half-life ~6-8 days ~30 minutes
GH pulse pattern Sustained, blunted Pulsatile, physiologic
Human trial data Limited but present Essentially absent
Peer-reviewed metabolic data Minimal Near zero

For a deeper look at why half-life differences matter in research design, see CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research.

Metabolic and Body-Composition Research: Where the Evidence Stands

Metabolic and Body-Composition Research: Where the Evidence Stands

Most published data on CJC‑1295 focus narrowly on GH and IGF‑1 elevation. The metabolic story, lipolysis, insulin sensitivity, visceral fat reduction, and lean mass accrual, is far less developed.

What is reasonably supported:

  • Elevated IGF‑1 is associated with improved nitrogen retention and lean tissue support in multiple GH-axis studies, though not specifically attributed to CJC‑1295 without DAC in controlled trials.
  • The DAC form has shown statistically significant IGF‑1 elevation lasting up to 28 days in early human dose-escalation work.
  • Tesamorelin, a distinct GHRH analog with an FDA-approved indication for HIV-associated lipodystrophy, provides the closest proxy for what sustained GHRH stimulation can do to visceral adipose tissue. Researchers comparing these agents should review Ipamorelin vs Tesamorelin for mechanistic context.

What remains speculative:

  • Direct fat-loss outcomes attributable to CJC‑1295 without DAC in healthy subjects.
  • Sleep quality improvements, often cited in community forums, have no controlled human data linking them specifically to either CJC‑1295 variant.
  • Insulin sensitivity modulation, plausible given GH's known effects on glucose metabolism, but unstudied for this peptide directly.

"The absence of evidence is not evidence of absence, but in a regulatory and safety context, it functions as one until trials are conducted."

Recovery Models, Stacking Protocols, and the Evidence Gap

Recovery Models, Stacking Protocols, and the Evidence Gap

Injury recovery is perhaps the most enthusiastically discussed application of CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models, and the one with the least formal support.

The theoretical basis is coherent. GH and IGF‑1 both play established roles in collagen synthesis, satellite cell activation, and connective tissue repair. If CJC‑1295 reliably elevates these signals, downstream recovery benefits are biologically plausible. The problem is the inferential leap from plausibility to protocol.

Stacking With Tesamorelin and Ipamorelin

A growing number of research models combine CJC‑1295 without DAC with either Tesamorelin or Ipamorelin to target complementary points on the GH axis. Multi-peptide blends designed for this purpose are available for research use, for example, formulations such as the Tesamorelin, AOD9604, CJC-1295, Ipamorelin 12mg blend represent how researchers are structuring combination protocols in 2026.

Key considerations for combination research models:

  • Receptor saturation: Stacking a GHRH analog with a GHRP creates synergistic GH release, but the ceiling effect and desensitization timeline are not well-mapped.
  • IGF‑1 overshoot risk: Sustained supraphysiologic IGF‑1 carries theoretical oncogenic and insulin-resistance concerns that no long-term CJC‑1295 trial has adequately addressed.
  • Protocol standardization: Community dosing is largely reverse-engineered from Tesamorelin clinical data. Researchers using Tesamorelin and CJC-1295 Ipamorelin 12mg blend formulations should treat dosing guidance as investigational, not clinical.
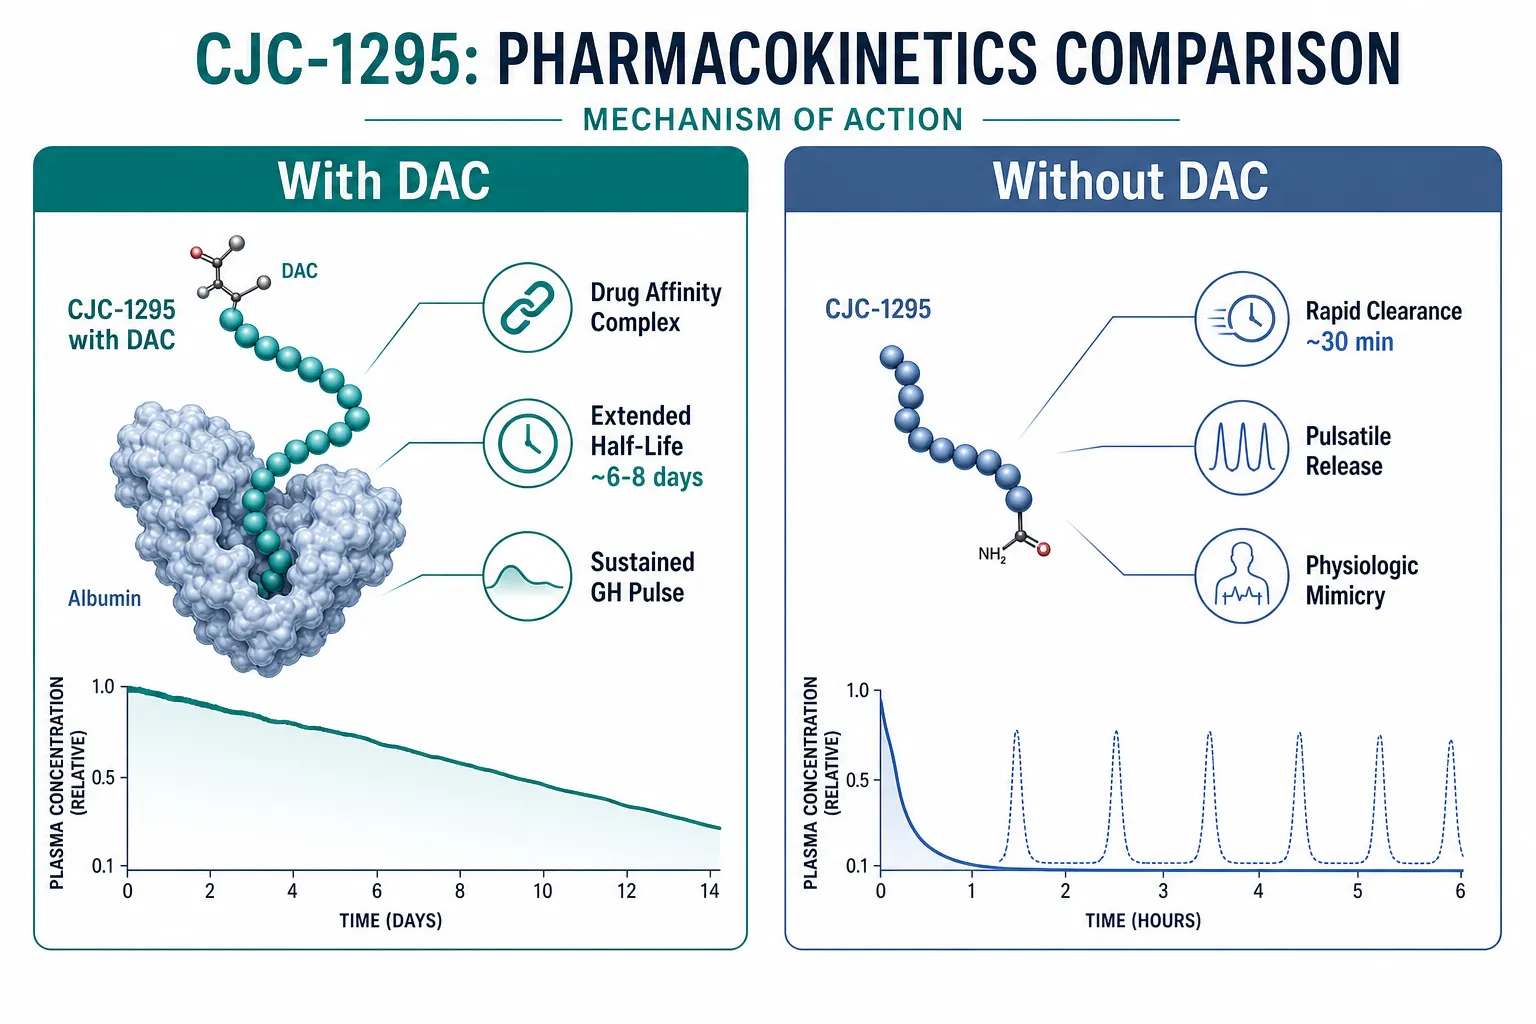
Regulatory and Purity Context in 2026

The FDA's tightened compounding restrictions between 2023 and 2026 have directly affected the availability and sourcing landscape for both CJC‑1295 variants. For any preclinical or in-vitro research application, purity verification through third-party Certificate of Analysis (CoA) documentation is non-negotiable. Resources on peptide CoA verification and high-purity peptide sourcing provide practical guidance for maintaining research integrity.

The clinical development program for CJC‑1295 was halted before Phase III completion, meaning no modern large-scale trial data exist. Sports and performance-enhancement literature in 2026 continues to flag both variants as prohibited substances under WADA rules, reinforcing their strictly investigational status.

Conclusion

CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models represents a field where biological plausibility has raced far ahead of controlled evidence. The pharmacokinetic distinction between the two variants is well-established; the metabolic, recovery, and sleep-related outcomes that dominate community discussion are not.

Actionable next steps for researchers and informed readers:

  1. Distinguish the variants clearly before designing any protocol, half-life differences make the two compounds functionally distinct research tools.
  2. Anchor expectations to Tesamorelin data when evaluating metabolic claims, as it provides the closest evidence-based proxy for GHRH analog effects on body composition.
  3. Prioritize purity verification, regulatory tightening in 2026 makes sourcing integrity a first-order concern, not an afterthought.
  4. Treat stacking protocols as hypothesis-generating, not validated, combination models with Ipamorelin or Tesamorelin are promising research directions, not proven therapies.
  5. Monitor the clinical trial landscape, the absence of modern Phase II/III data for either variant is the single largest obstacle to evidence-based application.

The questions surrounding CJC‑1295 beyond GH elevation are worth asking. Answering them rigorously will require the kind of controlled human research that, as of 2026, has yet to arrive.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-and-without-dac-beyond-growth-hormone-emerging-questions-in-metabo.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-29 13:09:222026-08-29 13:09:22CJC‑1295 With and Without DAC Beyond Growth Hormone: Emerging Questions in Metabolic and Recovery Research Models
Page 1 of 212
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top