Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: bpc-157

Research-Use Peptide Reviews: How to Audit Product Claims for BPC-157, TB-500, GHK-Cu, and Glow Blends

Research-Use Peptide Reviews: How to Audit Product Claims for BPC-157, TB-500, GHK-Cu, and Glow Blends

November 4, 2026/0 Comments/in Uncategorized/by

Only 30% of research peptide vendors tested in independent audits between 2023 and 2025 supplied products that matched both the labeled identity and stated purity. That gap between claim and reality makes reading a product page, or a glowing user review, a genuinely risky exercise. This guide on Research-Use Peptide Reviews: How to Audit Product Claims for BPC-157, TB-500, GHK-Cu, and Glow Blends walks through a structured method for separating credible data from marketing fiction, covering single agents and multi-peptide blends alike.

Key Takeaways

  • A Certificate of Analysis (COA) is only as reliable as the lab that issued it and the assay used to generate it.
  • BPC-157 and TB-500 have no approved human clinical trials and carry specific regulatory and anti-doping risks in 2026.
  • GHK-Cu has a narrow but real topical evidence base; injectable claims are largely extrapolated.
  • Multi-peptide "glow blends" almost never have blend-level clinical data, making individual-ingredient studies a poor substitute.
  • Matching a product claim to the specific assay type, species, and dose used in the source study is the single most useful audit step.

Understanding the Evidence Base Before Reading Any Review

Understanding the Evidence Base Before Reading Any Review

Before evaluating what a review says about a peptide, it helps to know what the underlying science actually supports. Each compound in this space sits at a different point on the evidence spectrum, and conflating them is the most common error in vendor marketing and user testimonials alike.

BPC-157 (body protection compound 157) has an extensive preclinical literature. Rodent studies show tissue-healing and gastroprotective effects. No peer-reviewed randomized controlled trials in humans have been published as of 2026. The FDA has not approved BPC-157 for any indication, and it remains on the agency's list of compounds for which compounding is not permitted without specific authorization. WADA does not currently list BPC-157 on its prohibited list, but that status is under active review.

TB-500 is a synthetic analog of thymosin beta-4. Like BPC-157, its evidence base is almost entirely animal and in-vitro. WADA explicitly prohibits thymosin beta-4 and its analogs, making TB-500 a banned substance in competitive sport. Under 2026 HHS guidance on enforcement discretion, it remains in a regulatory grey zone for compounders, meaning legitimate research use requires careful legal framing and appropriate disclaimers.

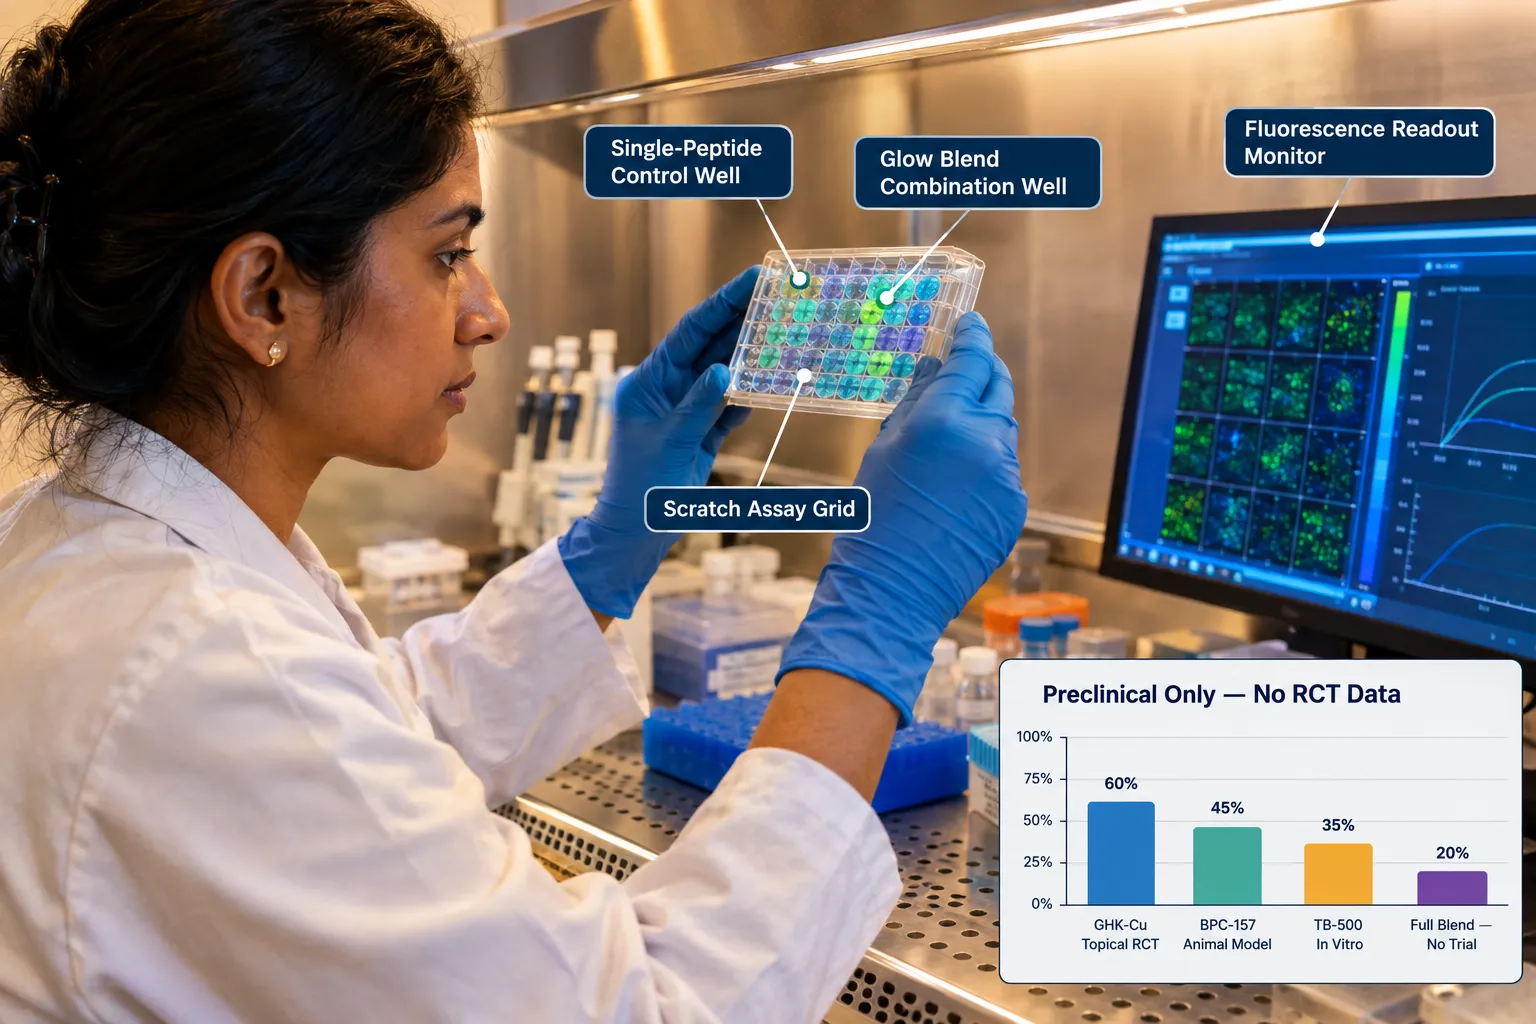
GHK-Cu (copper peptide) is the outlier. A published, peer-reviewed facial-cream trial, often called the Leyden study, demonstrated measurable improvements in skin parameters with topical application. That is a meaningful data point. It is not, however, evidence for injectables, systemic anti-aging effects, or the wound-healing benefits frequently promoted in vendor copy. The topical-to-injectable extrapolation is a significant logical leap, and regulators in several jurisdictions began scrutinizing injectable GHK-Cu marketing claims in late 2026.

Key distinction: A study that supports a mechanism is not the same as a study that supports a product claim. Audit every review against this filter first.

For context on how rigorous reference standards factor into compound verification, see this overview of Bachem and reference standards for building robust peptide benchmarks.


A Six-Step Audit Framework for Research-Use Peptide Reviews
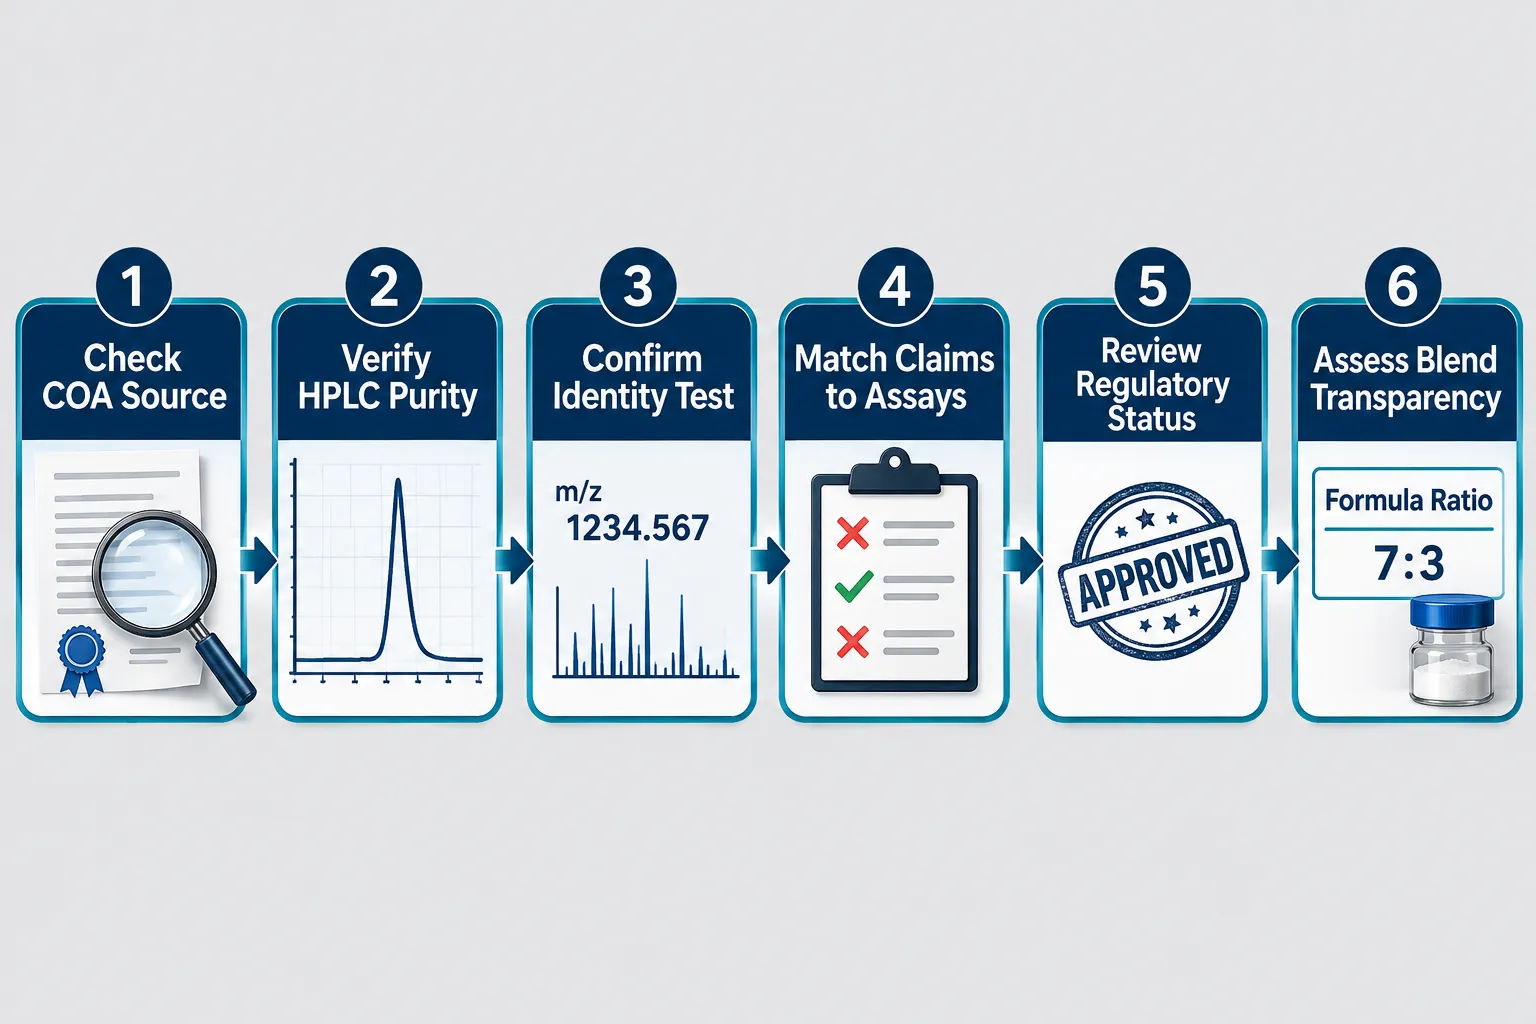
A Six-Step Audit Framework for Research-Use Peptide Reviews

Applying a consistent checklist to any research-use peptide review, whether from a vendor page, a forum post, or an aggregator site, quickly separates credible assessments from anecdote dressed as evidence.

Step 1: Demand a Third-Party COA, Not an In-House Document

A Certificate of Analysis generated by the selling vendor carries an obvious conflict of interest. The COA should come from an accredited independent laboratory. Check that the lab name is searchable, the report date matches the batch, and the document includes a unique lot number.

Step 2: Check the Assay Type Against the Claim

Assay What It Confirms What It Does Not Confirm
HPLC Purity percentage Correct amino acid sequence
Mass spectrometry Molecular identity Biological activity
Endotoxin test Sterility safety Efficacy

A product can pass purity testing at 99% and still be the wrong peptide. Identity confirmation via mass spectrometry is non-negotiable for injectable research compounds.

Step 3: Map Claims to the Actual Study Population

When a vendor cites a study, verify: Was it in rodents or humans? What was the route of administration? What was the dose? A rat-model study on subcutaneous BPC-157 does not validate a topical cream claim, and a topical GHK-Cu study does not validate an intravenous protocol.

Step 4: Evaluate Regulatory and Anti-Doping Risk Statements

Legitimate research-use vendors make explicit, accurate statements about regulatory status. Red flags include: no disclaimer at all, language implying FDA approval, or the absence of WADA prohibition notices on TB-500 products. For researchers interested in related compounds navigating similar regulatory considerations, the SS-31 10mg research peptide considerations page offers a useful parallel framework.

Step 5: Scrutinize User Review Language

User reviews for research peptides frequently describe personal health outcomes. Under current US law, this constitutes an efficacy claim if it appears on a commercial platform and the vendor amplifies it. Reviews using clinical language ("healed my tendon," "restored hair density") without research framing are a compliance signal worth noting. Comparable context appears in the tesa peptide benefits discussion, which demonstrates how to present mechanistic information responsibly.

Step 6: Cross-Reference with Anti-Doping Databases

For TB-500, WADA's current prohibited list is the starting point. Any review that omits this information for a sports-active audience is incomplete at best and misleading at worst.


Auditing Multi-Peptide "Glow Blends", A Higher Standard Required

Multi-peptide cosmetic blends, often marketed with terms like "glow blend," "skin stack," or "repair complex", present additional audit challenges. Research-use peptide reviews for blends require a fundamentally different lens than single-agent reviews.

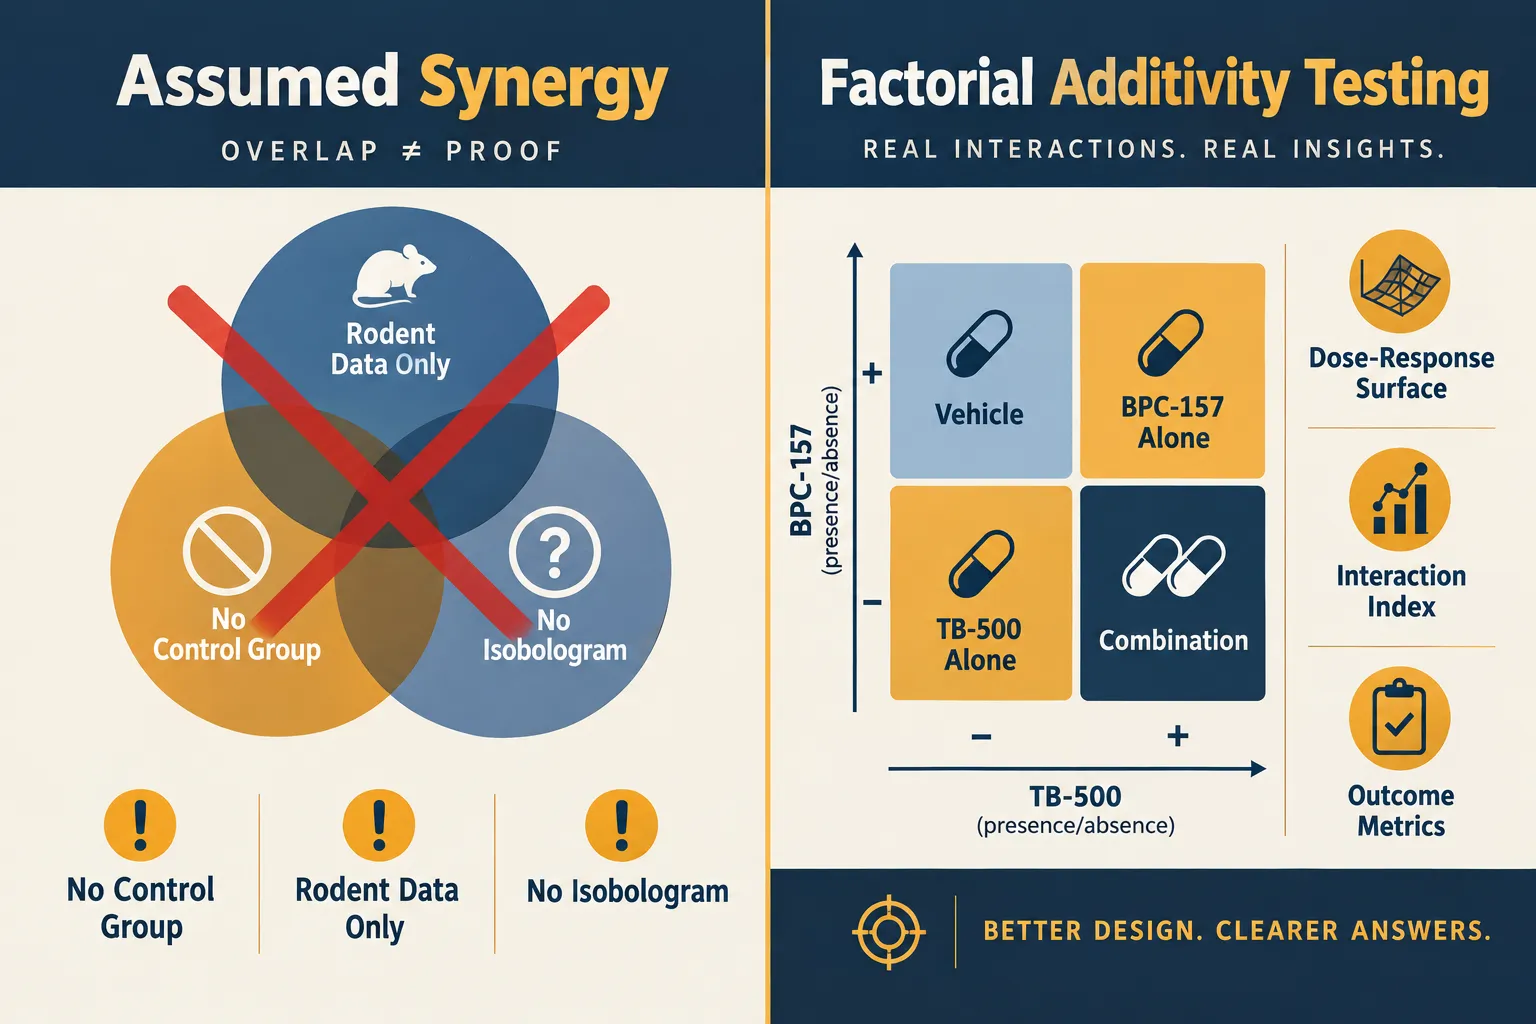
The core problem: No blend-level clinical trial exists for any commercially available peptide combination product as of 2026. Vendors assemble ingredients with individual study support and imply synergy without demonstrating it. This is not a minor gap, peptide interactions can be additive, neutral, or antagonistic depending on concentration and delivery vehicle.

What to look for in a credible blend review:

  • Disclosure of individual peptide concentrations per dose
  • Separate COA entries for each active ingredient
  • Explicit acknowledgment that blend-level data does not exist
  • Avoidance of phrases like "clinically proven formula" when only isolated ingredients have been studied

Common design flaws in blend trials cited by vendors:

  1. No control group or placebo arm
  2. Participant self-selection bias
  3. Outcome measures that are subjective (self-rated skin texture)
  4. Confounding co-interventions (concurrent skincare regimen not controlled)

Researchers exploring other compound categories with similar complexity, such as GLP-related peptides, will recognize these same issues in blend formulations. The GLP-3 peptide signaling pathway article illustrates how even well-characterized peptide mechanisms require careful interpretation before extrapolating to formulated products.

For aging-support research contexts, aging support peptide categories provide a useful reference for understanding how compounds are categorized without overstating their clinical status.


Conclusion

Research-use peptide reviews are only useful when read alongside hard documentation: verified third-party COAs with identity confirmation, honest regulatory status disclosures, and a clear match between cited evidence and the actual claim being made. BPC-157 and TB-500 sit firmly in preclinical territory, with significant regulatory and anti-doping implications. GHK-Cu has limited but real topical data that vendors routinely overextend. Multi-peptide glow blends require the strictest scrutiny of all, because blend-level evidence simply does not exist.

Actionable next steps for anyone auditing research-use peptide reviews:

  1. Download the COA before reading the review, let the documentation set the baseline.
  2. Identify the assay type and confirm it includes both purity and identity testing.
  3. Pull the cited study and check species, route, and dose against the product claim.
  4. Search WADA's current prohibited list for any compound before use in sport contexts.
  5. For blends, demand per-ingredient concentration disclosure as a minimum requirement.

Applying this framework consistently transforms a landscape of promotional noise into something researchable and actionable.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/research-use-peptide-reviews-how-to-audit-product-claims-for-bpc-157-tb-500-ghk.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-04 14:05:472026-11-04 14:05:47Research-Use Peptide Reviews: How to Audit Product Claims for BPC-157, TB-500, GHK-Cu, and Glow Blends
What Is BPC-157? A Research Guide to Barrier Function, Angiogenesis, and Tissue-Repair Readouts

What Is BPC-157? A Research Guide to Barrier Function, Angiogenesis, and Tissue-Repair Readouts

November 1, 2026/0 Comments/in Uncategorized/by

Fewer than two dozen human participants have completed controlled trials on BPC-157, yet this 15-amino-acid peptide now appears in sports recovery forums, military wellness programs, and compounding pharmacy catalogs across the United States. That gap between limited clinical evidence and widespread interest makes a clear-headed, mechanism-focused explainer essential for researchers and informed readers alike.

This guide to What Is BPC-157? A Research Guide to Barrier Function, Angiogenesis, and Tissue-Repair Readouts separates molecular hypotheses from measurable laboratory assays across four key research models: epithelial, vascular, tendon, and gastrointestinal tissue.

Key Takeaways

  • BPC-157 is a synthetic pentadecapeptide derived from a human gastric juice protein, studied primarily in preclinical (animal and cell) models.
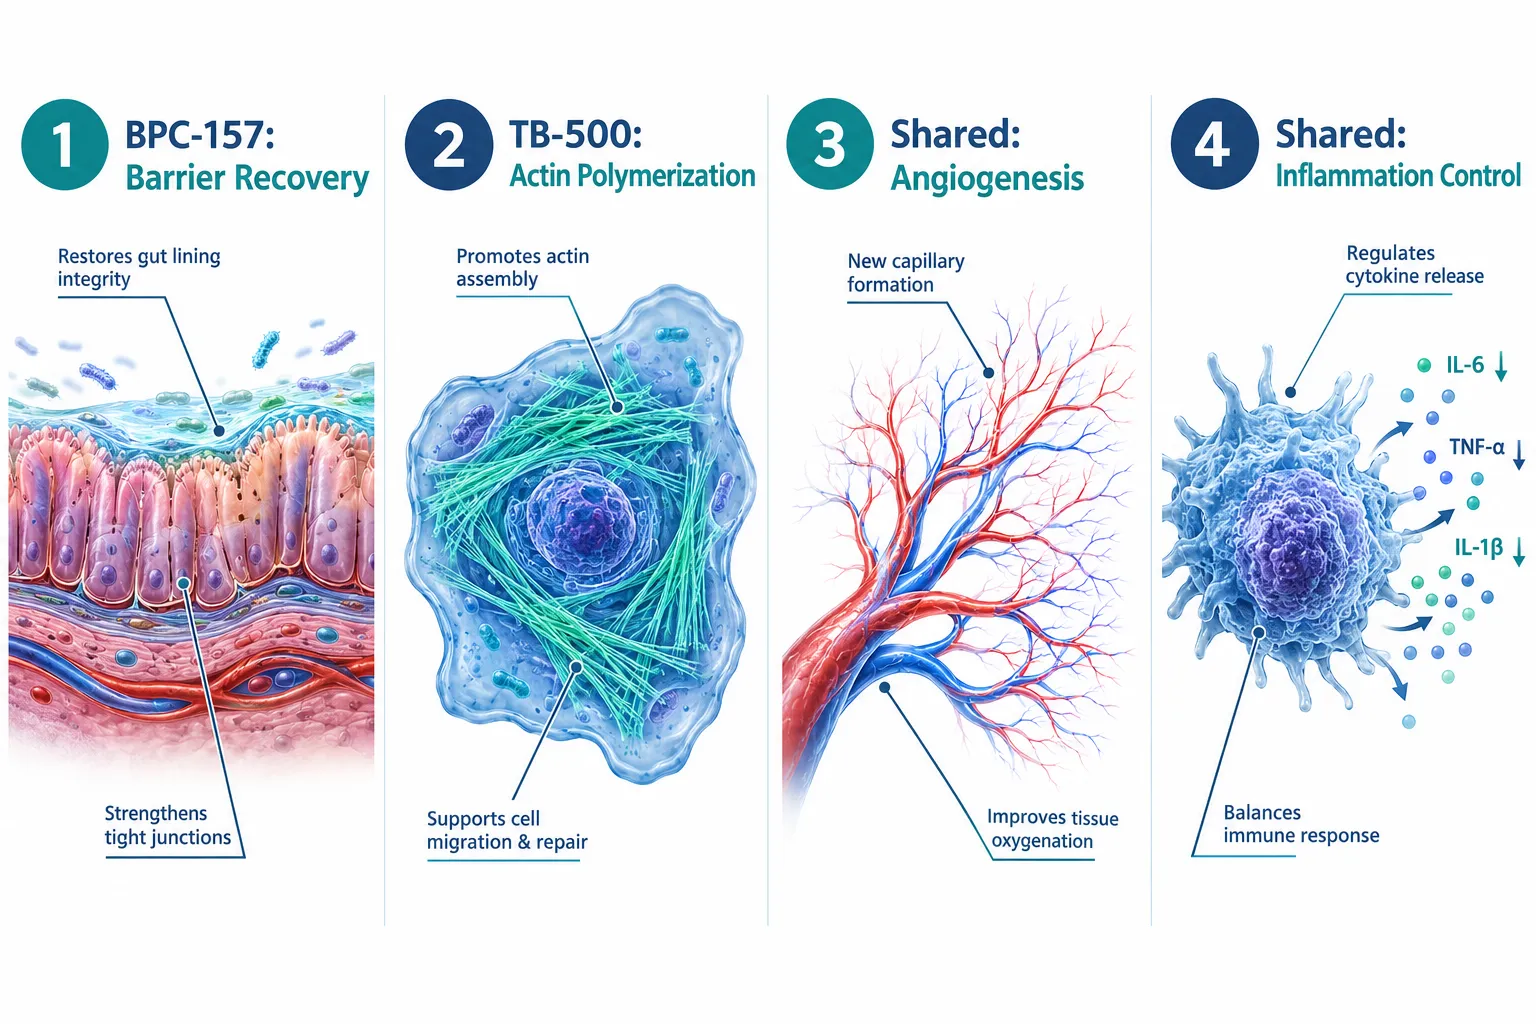
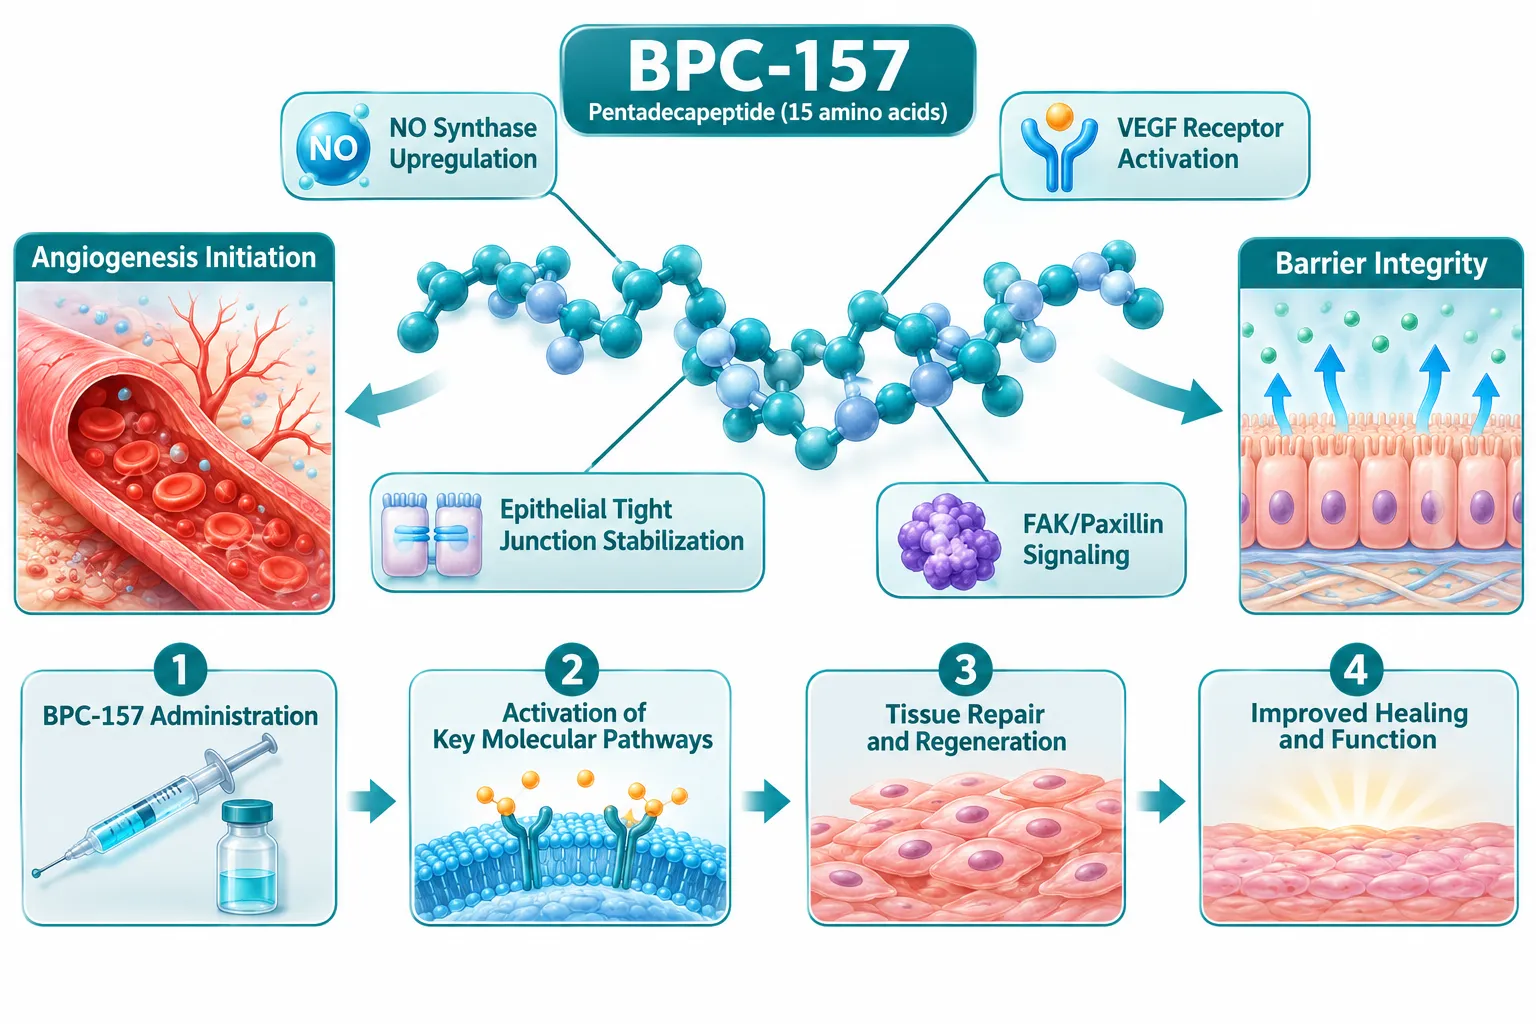
  • Its most documented mechanisms involve nitric oxide (NO) system modulation, VEGF-driven angiogenesis, and tight-junction stabilization.
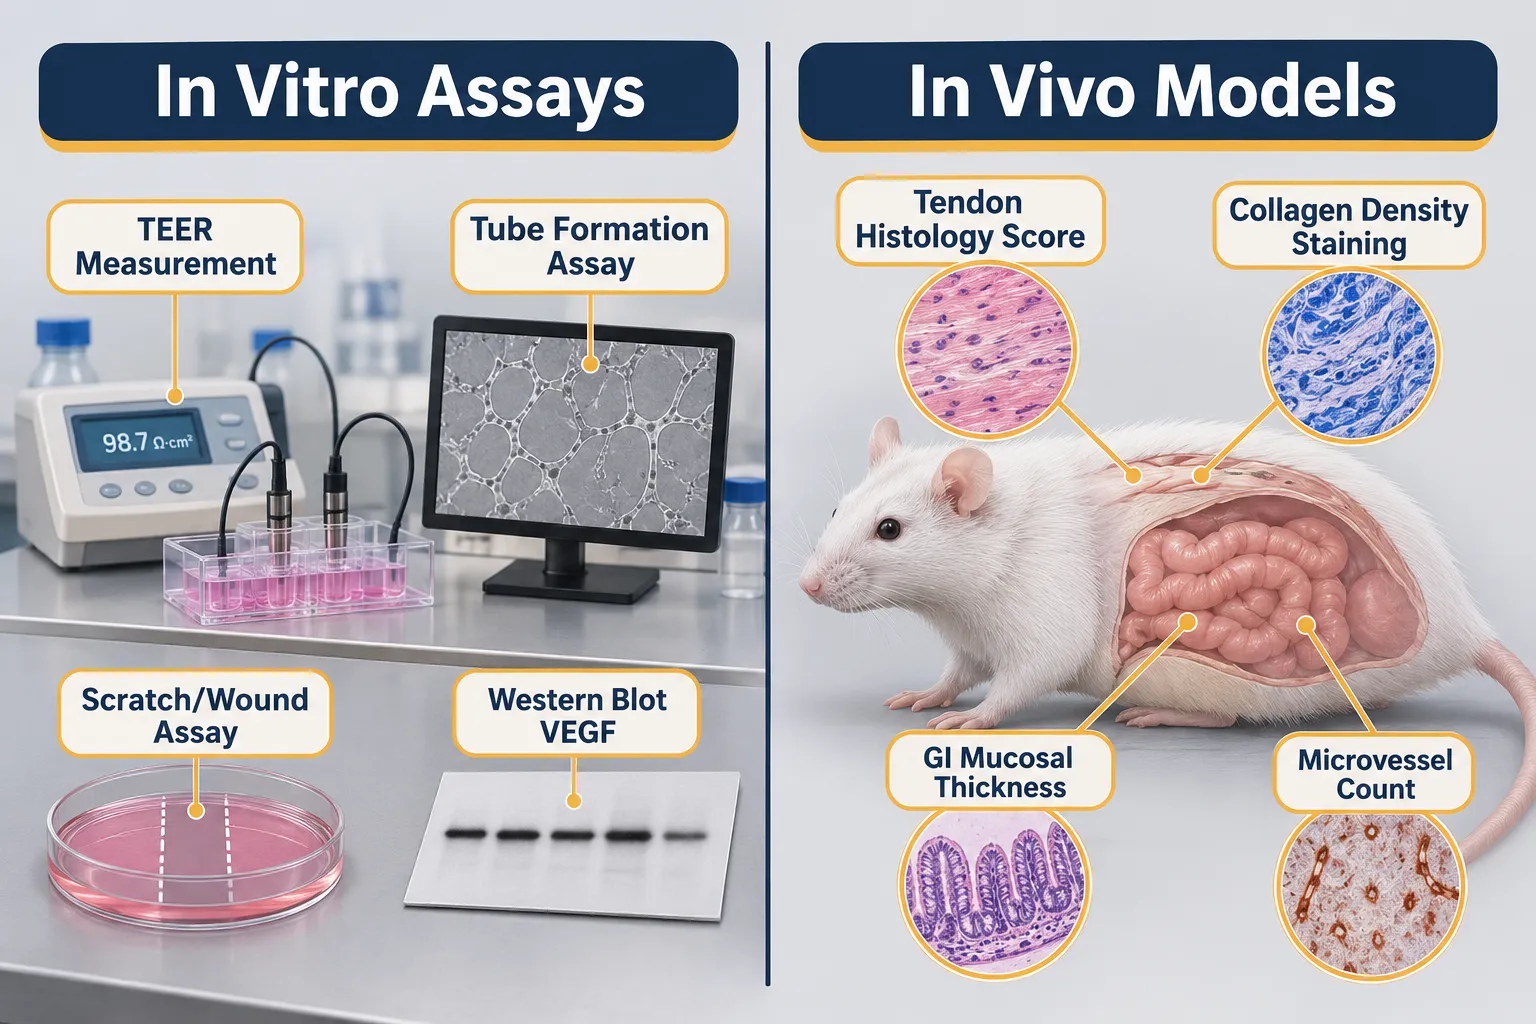
  • Measurable assays, TEER, tube-formation, scratch assays, and histological scoring, are the practical tools researchers use to evaluate these effects.
  • Human clinical data remain sparse, with ongoing trials as of 2026 still in early phases.
  • Regulatory status is unresolved; the FDA has expressed skepticism, and WADA has banned the peptide in competitive sport.

Core Biology: What BPC-157 Is and Where It Comes From

BPC-157 (Body Protection Compound-157) is a synthetic, stable pentadecapeptide consisting of 15 amino acids. Researchers derived its sequence from a larger protein found in human gastric juice. The "stable" designation is important: unlike many peptides, BPC-157 retains its structure in aqueous solution, making it practical for cell culture and animal studies.

Core Biology: What BPC-157 Is and Where It Comes From

The peptide does not bind to a single, well-characterized receptor in the way classical drugs do. Instead, preclinical evidence points to three overlapping mechanistic axes:

  1. Nitric Oxide (NO) system modulation, BPC-157 appears to influence endothelial NO synthase (eNOS) activity, which regulates vasodilation, vascular permeability, and cellular survival signals.
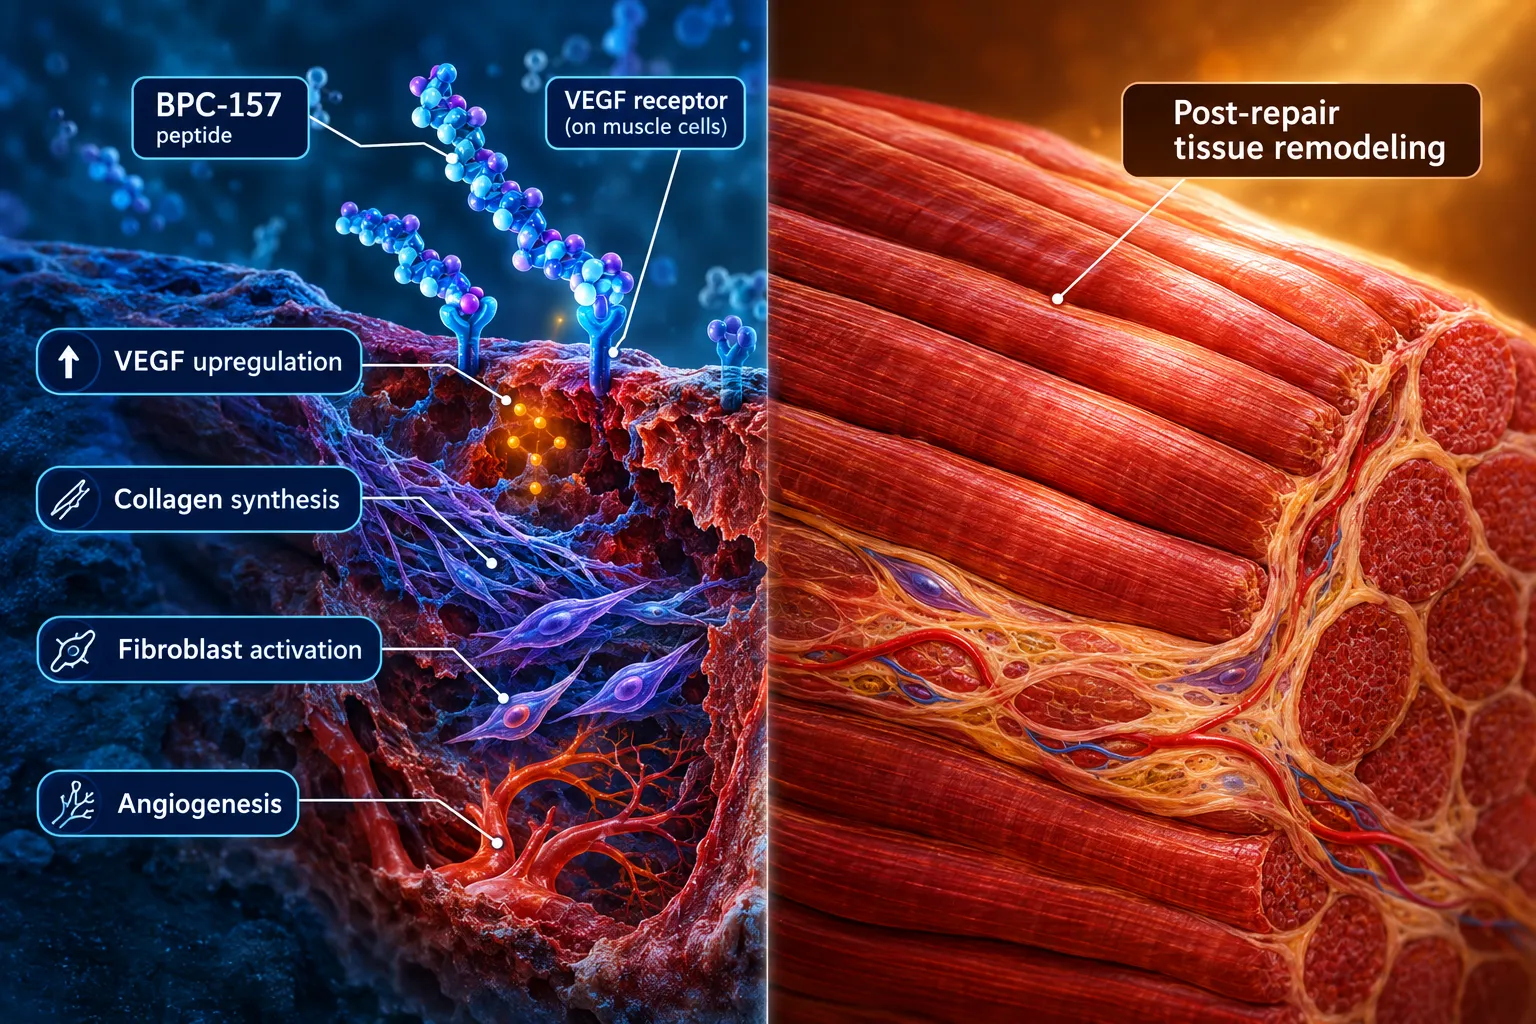
  2. Growth factor cross-talk, Studies report upregulation of vascular endothelial growth factor (VEGF) and its receptors, a key step in new blood vessel formation.
  3. Cytoskeletal and adhesion signaling, Evidence from tendon and gut models implicates FAK (focal adhesion kinase) and paxillin pathways, which govern how cells attach to their surroundings and migrate during repair.

These three axes are not mutually exclusive. In gastrointestinal models, for example, NO modulation and VEGF cross-talk appear to work together to accelerate mucosal healing. Understanding which axis dominates in a given tissue type is a central challenge for researchers designing assays.


Measuring the Key Effects: Assays Across Tissue Models

Understanding What Is BPC-157? A Research Guide to Barrier Function, Angiogenesis, and Tissue-Repair Readouts requires knowing which laboratory tools actually capture its effects. Each proposed mechanism maps onto specific, reproducible readouts.

Measuring the Key Effects: Assays Across Tissue Models

Barrier Function Readouts

Barrier function refers to a tissue's ability to restrict unwanted passage of molecules and pathogens between compartments. For BPC-157 research, two models dominate:

  • Intestinal epithelial monolayers, Researchers grow Caco-2 or T84 cells on permeable supports and measure Trans-Epithelial Electrical Resistance (TEER). Higher TEER signals tighter junctions. BPC-157-treated monolayers in several preclinical reports show increased TEER alongside elevated expression of claudin and occludin, the proteins that physically seal tight junctions.
  • Gastric mucosal models, In rodent studies, barrier integrity is assessed histologically by measuring mucosal thickness, goblet cell density, and the depth of stress-induced lesions.

Pull quote: "TEER measurement remains the gold-standard in vitro readout for peptide-driven barrier restoration, it is quantitative, reproducible, and translatable across cell lines."

Angiogenesis Readouts

Angiogenesis, the sprouting of new blood vessels from existing ones, is central to tissue repair because oxygen and nutrient delivery must keep pace with cellular proliferation. Key assays include:

Assay What It Measures Model Type
Tube formation (Matrigel) Endothelial cell network assembly In vitro
Scratch / wound-closure Cell migration rate In vitro
Aortic ring sprouting Vessel outgrowth ex vivo Ex vivo
Microvessel density staining CD31+ vessel count per field In vivo

Emerging 2026 work has focused on the FBXO22-BACH1 axis, a ubiquitin-proteasome pathway that regulates transcription factors controlling angiogenic gene expression. Early data suggest BPC-157 may influence BACH1 degradation, freeing pro-angiogenic target genes. This is a molecular hypothesis requiring further validation, but it represents a more precise mechanistic target than earlier general VEGF claims.

Tendon and Musculoskeletal Readouts

Tendon healing is slow and scar-prone. In rodent Achilles and rotator-cuff transection models, BPC-157 effects are quantified through:

  • Histological collagen scoring (Bonar scale or custom rubric)
  • Biomechanical load-to-failure testing
  • Immunohistochemistry for tenascin-C and type I/III collagen ratio

Results across multiple rodent studies are generally positive, but editorials published through 2026 have flagged concerns about study design quality, small sample sizes, and the absence of large-animal or human replication. A recurring phrase in expert commentary is "Regeneration or Risk?", highlighting that accelerating cell proliferation in poorly controlled conditions could theoretically promote fibrosis rather than true regeneration.


Regulatory Landscape and Research Outlook in 2026

The regulatory and competitive sport context shapes how researchers must frame their work. As of late 2026:

  • The FDA has not approved BPC-157 for any indication and has expressed explicit skepticism about compounding pharmacy preparations. An advisory committee vote on compounded peptides earlier this year reflected significant caution.
  • WADA lists BPC-157 as a prohibited substance in competition, classifying it under peptide hormones and growth factors. Sports researchers and athletes face strict prohibitions.
  • Off-label use continues to grow despite no approval, driven largely by anecdotal reports and social media visibility.

Regulatory Landscape and Research Outlook in 2026

Clinical trials registered as of 2026 remain in early phases, targeting gastrointestinal conditions such as inflammatory bowel disease and post-surgical mucosal healing. Dentistry has emerged as an exploratory niche, with pilot-scale work examining BPC-157 effects on periodontal barrier tissue. For researchers comparing peptide study designs, context from related compounds like SS-31 peptide research considerations or LL-37 versus SS-31 benefits can inform assay selection and controls.

Understanding broader peptide categories also helps place BPC-157 in context. Researchers studying metabolic and tissue-repair agents may find comparative value in resources on what constitutes the strongest peptide for weight loss or the design considerations behind CJC1295 Ipamorelin dosage protocols. For those sourcing verified compounds for preclinical work, reviewing lab-tested peptides supply standards is an important step. Additionally, comparing growth hormone-axis peptides such as tesa versus sermorelin illustrates how different peptide classes target overlapping but distinct tissue-repair pathways.


Conclusion

What Is BPC-157? A Research Guide to Barrier Function, Angiogenesis, and Tissue-Repair Readouts ultimately points to a peptide with a rich preclinical profile and a thin clinical one. The molecular mechanisms, NO-system modulation, VEGF-pathway activation, tight-junction reinforcement, and the emerging FBXO22-BACH1 angiogenesis axis, are scientifically plausible and measurable with established assays.

Actionable next steps for researchers:

  • Prioritize assay selection based on the specific tissue model: TEER for barrier studies, tube-formation and microvessel density for angiogenesis, Bonar scoring for tendon.
  • Apply rigorous controls and pre-register study designs to address the reproducibility concerns flagged in 2026 expert commentary.
  • Monitor FDA and WADA guidance updates before designing any translational or human-adjacent protocol.
  • Treat FBXO22-BACH1 data as a hypothesis-generating finding requiring independent replication.
  • Cross-reference BPC-157 findings with structurally distinct cytoprotective peptides to build comparative mechanistic understanding.

The evidence base is growing, but the gap between preclinical promise and human-validated outcomes remains wide. Disciplined assay design and transparent reporting are the tools that will close it.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/what-is-bpc-157-a-research-guide-to-barrier-function-angiogenesis-and-tissue-rep.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-01 14:04:052026-11-01 14:04:05What Is BPC-157? A Research Guide to Barrier Function, Angiogenesis, and Tissue-Repair Readouts
Glow Blend (GHK-Cu / BPC-157 / TB-500) In Vitro Fibroblast Migration Assays: Matrix Metalloproteinase Readouts

Glow Blend (GHK-Cu / BPC-157 / TB-500) In Vitro Fibroblast Migration Assays: Matrix Metalloproteinase Readouts

October 30, 2026/0 Comments/in Uncategorized/by

Collagen type I/III ratios are among the most clinically meaningful markers of dermal tissue quality, and the idea of shifting that ratio upward using a precisely formulated multi-peptide blend is now driving active interest among laboratory researchers. The Glow Blend (GHK-Cu / BPC-157 / TB-500) in vitro fibroblast migration assays: matrix metalloproteinase readouts framework sits at the intersection of peptide biochemistry, extracellular matrix (ECM) science, and scratch-wound modeling. As 2026 research-supply catalogs list a standardized 70 mg lyophilized vial (50 mg GHK-Cu, 10 mg BPC-157, 10 mg TB-500), the scientific rationale for pairing these three peptides in cell-based assays becomes worth examining in detail.

Key Takeaways

  • The Glow Blend combines GHK-Cu, BPC-157, and TB-500 in a single research-grade vial designed for in vitro and non-clinical ECM and migration studies.
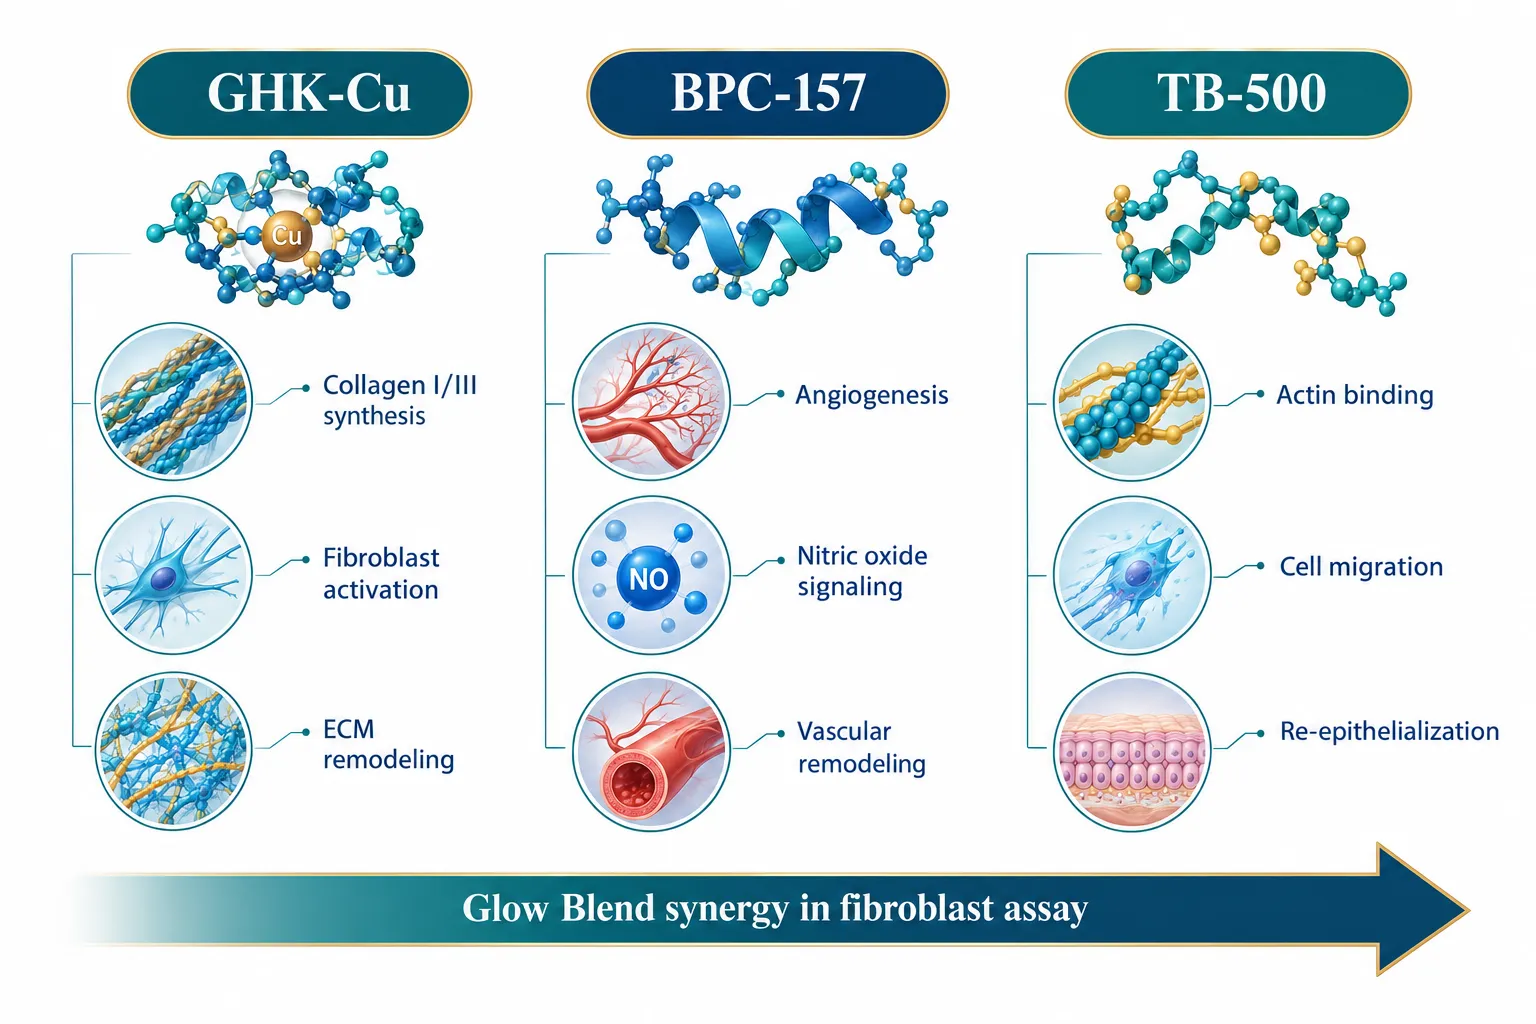
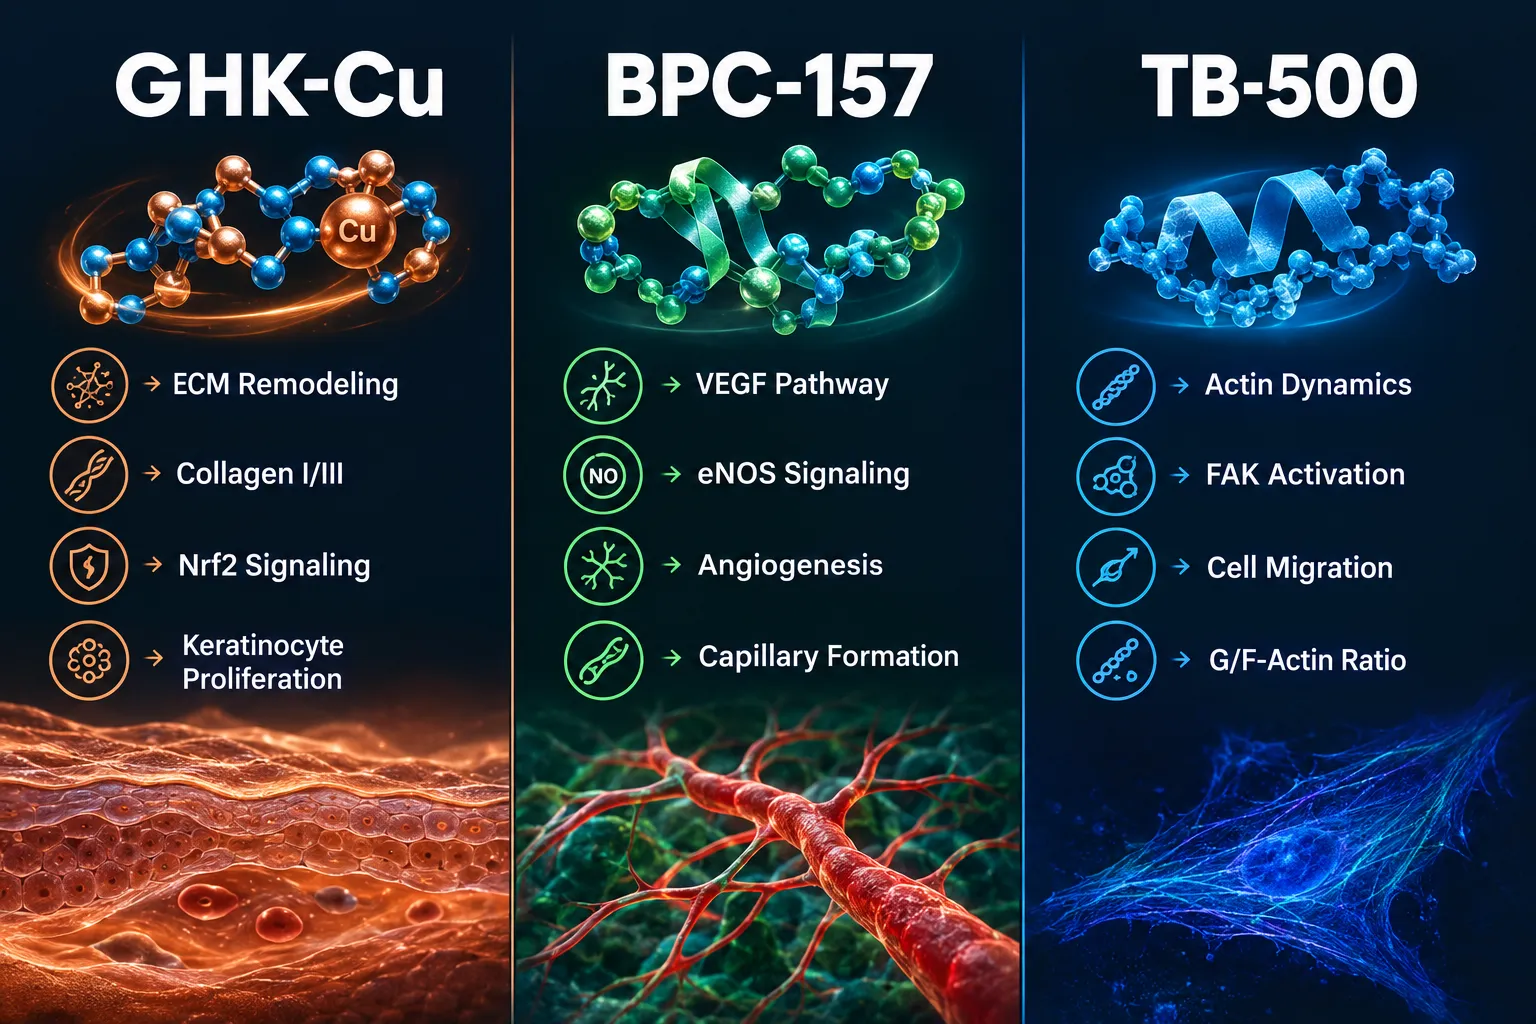
  • Each peptide operates through a distinct mechanism: GHK-Cu drives collagen and elastin synthesis, BPC-157 supports angiogenesis and tissue remodeling, and TB-500 mediates actin-dependent cell migration.
  • MMP-2 suppression and an elevated collagen I/III ratio are the two most theoretically relevant readouts when studying this blend in fibroblast scratch-wound assays.
  • No publicly available, controlled dataset yet reports numerical MMP-2 or MMP-9 fold-change values specific to the Glow Blend combination; current expectations are model-based.
  • All Glow Blend work is research-only; the combination has not been evaluated in controlled human trials.

Mechanism of Action: What Each Component Brings to Fibroblast Assays

Mechanism of Action: What Each Component Brings to Fibroblast Assays

Understanding the Glow Blend (GHK-Cu / BPC-157 / TB-500) in vitro fibroblast migration assays: matrix metalloproteinase readouts model requires separating what each peptide does at the cellular level before asking what their combination might do.

GHK-Cu (copper tripeptide) is a naturally occurring molecule with well-documented roles in collagen, elastin, and glycosaminoglycan synthesis. Animal wound-healing studies show enhanced wound contraction, elevated granulation tissue, and activated fibroblasts in GHK-Cu-treated wounds compared to controls. Its relevance to MMP biology is significant: GHK-Cu has been linked to both stimulating early matrix remodeling enzymes and, at later repair phases, helping to temper destructive MMP activity. The net effect in well-designed fibroblast assays is a favorable shift in the collagen I/III ratio, an indicator of mature, load-bearing scar tissue replacing fragile early-repair matrix.

BPC-157 is a 15-residue gastric protein fragment studied across a range of preclinical models. Its principal contributions to a fibroblast assay context are angiogenic (through nitric-oxide signaling pathways) and inflammatory-modulatory. By promoting vessel formation and dampening pro-inflammatory mediators that upregulate MMP-9, BPC-157 adds a vascular and regulatory dimension that single-peptide GHK-Cu studies cannot capture.

TB-500 (a thymosin beta-4 fragment) is an actin-sequestering peptide. Its role in cell migration is probably the most mechanistically direct of the three. Preclinical wound models using TB-500 alone report re-epithelialization rate increases of roughly 42% by day 4 and 61% by day 7 versus saline controls. At concentrations as low as 10 picograms, keratinocyte migration in culture assays can increase two- to threefold. In scratch-wound assays, this translates to faster wound closure, the primary visual endpoint researchers capture via time-lapse microscopy before moving to MMP quantification.

Peptide Primary Assay Mechanism Relevant MMP Connection
GHK-Cu Collagen/elastin synthesis, fibroblast activation MMP-2 modulation, ECM maturation
BPC-157 Angiogenesis, nitric oxide signaling MMP-9 suppression (inflammatory axis)
TB-500 Actin-mediated cell migration, proliferation Indirect via ECM remodeling support

Designing the Assay: Scratch-Wound Protocol and MMP Readout Selection

Designing the Assay: Scratch-Wound Protocol and MMP Readout Selection

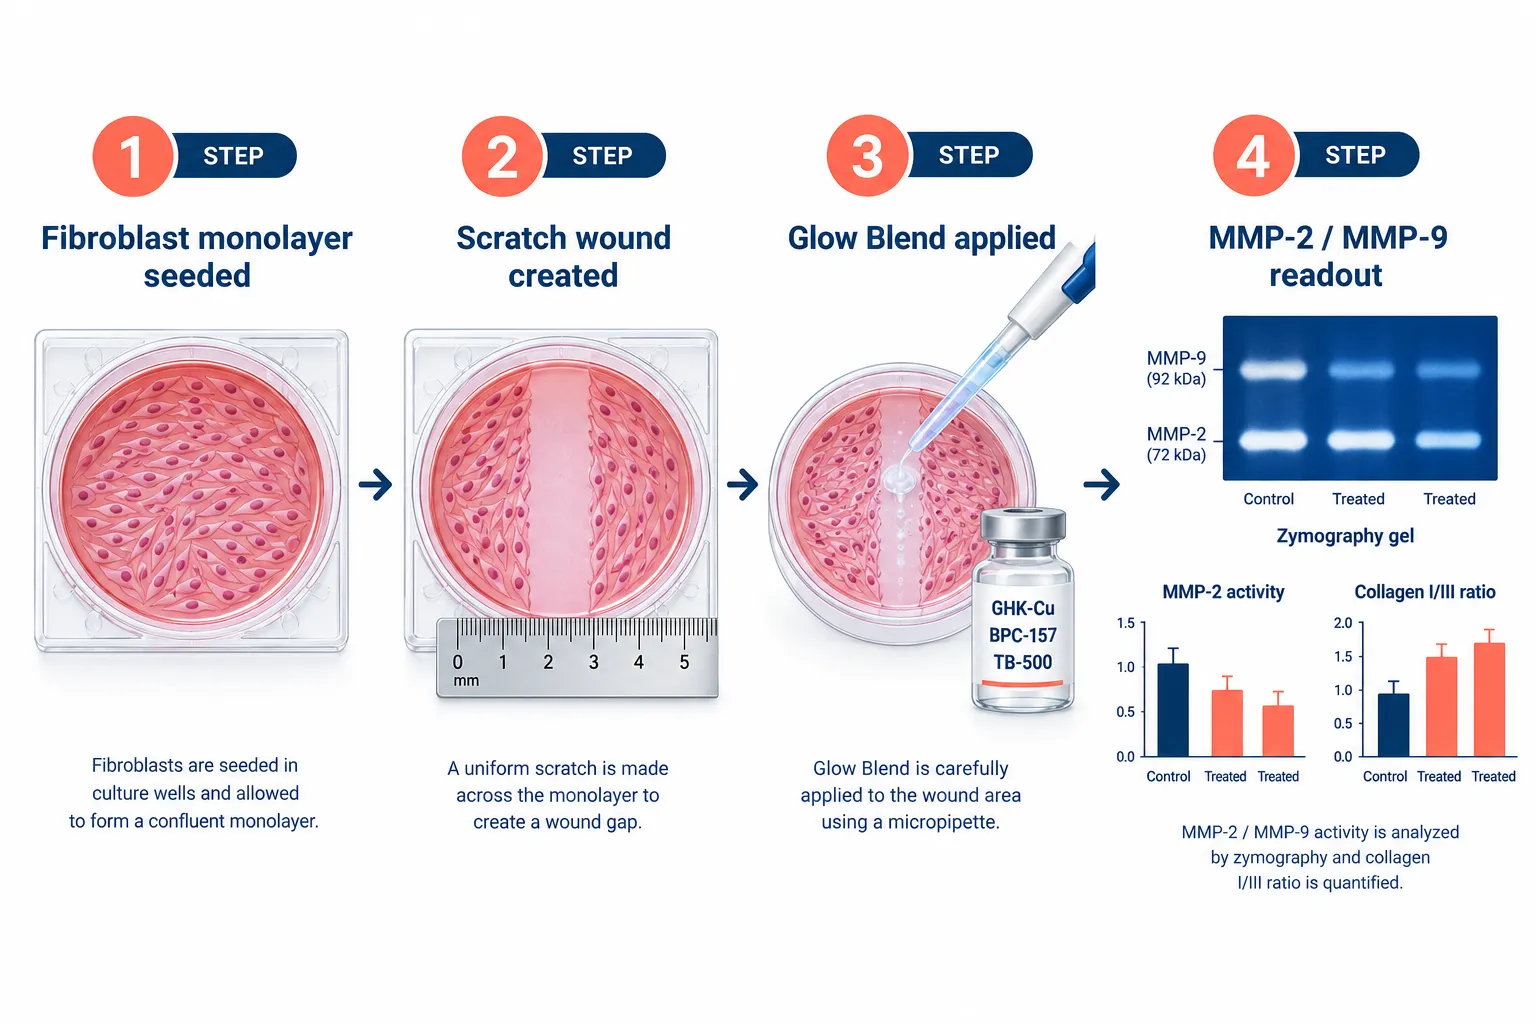
A rigorous Glow Blend (GHK-Cu / BPC-157 / TB-500) in vitro fibroblast migration assay begins with selecting an appropriate cell line. Primary human dermal fibroblasts (HDFs) or NIH 3T3 cells are the most commonly used models for collagen synthesis and MMP activity studies. After seeding to confluence, a standardized scratch is made with a pipette tip, media is changed to serum-reduced conditions to minimize confounding growth-factor signals, and the Glow Blend is introduced at defined concentration ranges.

Key readout decisions:

  • MMP-2 (gelatinase A): This is the primary MMP of interest. MMP-2 degrades type IV collagen and denatured collagens; its activity level determines whether the ECM environment favors cell migration or matrix stabilization. Gelatin zymography or fluorescent substrate ELISA are the standard quantification tools.
  • MMP-9 (gelatinase B): Often elevated in inflammatory conditions, MMP-9 can counteract collagen deposition. BPC-157's anti-inflammatory properties make MMP-9 suppression a plausible secondary endpoint.
  • Collagen I/III ratio: Measured via immunofluorescence staining or western blot, this ratio distinguishes mature dermal remodeling (type I dominant) from early provisional matrix (type III dominant).

"The strongest experimental design for this blend will include both gap-closure imaging and concurrent MMP zymography, run in parallel time points at 24, 48, and 72 hours post-treatment."

Critically, no vendor or published laboratory has yet released a peer-reviewed or publicly documented dataset reporting numerical MMP-2 or MMP-9 fold-change values for the Glow Blend as a combination. Any current expectations are extrapolations from single-peptide data. Researchers sourcing GHK-Cu for these studies may also find value in reviewing this GHK-Cu peptide purchase and copper peptide research sourcing guide for purity and formulation considerations.

Those working on complementary ECM and wound-healing models may also find relevant mechanistic context in wound healing research and in VEGF upregulation studies, both of which intersect directly with the angiogenic component that BPC-157 contributes to a Glow Blend assay.


Interpreting Results: MMP-2 Suppression and Collagen I/III Upregulation

Interpreting Results: MMP-2 Suppression and Collagen I/III Upregulation

When running Glow Blend (GHK-Cu / BPC-157 / TB-500) in vitro fibroblast migration assays: matrix metalloproteinase readouts, the expected pattern, based on individual peptide data, is a biphasic MMP-2 profile: an early, modest elevation supporting initial cell migration, followed by suppression as collagen deposition consolidates. This mirrors physiological wound repair, where MMP activity is needed transiently to clear matrix debris but must be downregulated to allow scar maturation.

Predicted outcome summary:

  • Faster scratch-wound closure versus vehicle control (TB-500 contribution)
  • Reduced MMP-2 and MMP-9 activity at 48-72 hours (GHK-Cu and BPC-157 contribution)
  • Higher collagen type I expression and improved I/III ratio by 72 hours (GHK-Cu primary driver)
  • Increased tube formation in co-culture or conditioned media models (BPC-157 contribution)

Researchers comparing multi-peptide blends with single-agent controls should also consider how formulation quality affects these outcomes. Benchmarking against certified reference peptides is essential; the article on Bachem and reference standards for robust peptide benchmarks outlines why purity validation matters for interpreting assay variability.

For labs interested in broader peptide research portfolios that include anti-aging and cellular repair models, exploring aging support research peptides provides additional context on how ECM-targeting compounds fit within a broader framework.

It is also worth noting that the Glow Blend has not been evaluated in controlled human trials. All interpretations of fibroblast migration and MMP data remain preclinical. Researchers seeking related multi-peptide blend research designs may also reference the Hulk Blend as a contrast case in multi-peptide combination research.


Conclusion

The Glow Blend (GHK-Cu / BPC-157 / TB-500) represents a rationally designed multi-peptide tool for researchers studying ECM dynamics, fibroblast behavior, and MMP regulation. The theoretical case for using this blend in scratch-wound and transwell migration assays is strong: each peptide addresses a distinct bottleneck in the tissue repair cascade, and together they could produce a more complete model of dermal remodeling than any single agent allows.

Actionable next steps for researchers:

  1. Source research-grade Glow Blend with documented purity from a verified supplier and confirm component ratios before assay design.
  2. Run dose-response curves for each peptide individually before combining, to establish baseline MMP-2 and collagen I/III values.
  3. Use gelatin zymography alongside scratch-wound imaging at 24, 48, and 72 hours to capture the full MMP activity timeline.
  4. Include a positive control (e.g., TGF-beta1 for collagen induction) and a negative control (vehicle only) in every plate.
  5. Publish or pre-register protocols openly, the field needs validated, Glow Blend-specific MMP datasets to move beyond single-peptide extrapolation.

The data gap is also an opportunity. The first well-controlled, publicly available fibroblast migration plus MMP readout study for this blend will become a key reference point for the peptide research community in 2026 and beyond.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/glow-blend-ghk-cu-bpc-157-tb-500-in-vitro-fibroblast-migration-assays-matrix-met.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-30 13:05:042026-10-30 13:05:04Glow Blend (GHK-Cu / BPC-157 / TB-500) In Vitro Fibroblast Migration Assays: Matrix Metalloproteinase Readouts
Ketorolac NSAID Suppression vs. BPC-157 Healing Signaling: Acute Phase Prostaglandin Modulation in Tendon Research

Ketorolac NSAID Suppression vs. BPC-157 Healing Signaling: Acute Phase Prostaglandin Modulation in Tendon Research

October 29, 2026/0 Comments/in Uncategorized/by

Tendon injuries account for roughly 30 percent of all musculoskeletal consultations worldwide, yet the standard pharmacological response, reach for an NSAID, may directly conflict with the biological signals that drive repair. The contrast between Ketorolac NSAID Suppression vs. BPC-157 Healing Signaling: Acute Phase Prostaglandin Modulation in Tendon Research sits at the center of a growing debate in regenerative sports medicine: should clinicians suppress the acute inflammatory cascade, or support it?

Key Takeaways

  • Ketorolac is a nonselective COX-1/COX-2 inhibitor that reduces prostaglandins, lowers pain, and dampens the acute inflammatory cascade in tendon tissue.
  • BPC-157 is a synthetic peptide that activates fibroblast proliferation, FAK-paxillin signaling, VEGF-driven angiogenesis, and collagen remodeling, pathways distinct from prostaglandin modulation.
  • The two agents target different biological layers of acute tendon repair, making direct pharmacological antagonism theoretically plausible but not yet documented in any tendon-specific study.
  • Nearly all BPC-157 data are preclinical; human efficacy and safety remain unestablished, and no regulatory body has approved it for musculoskeletal indications as of 2026.
  • Researchers and clinicians must weigh short-term analgesic benefits of NSAIDs against the possibility that prostaglandin suppression during days 1-4 post-injury may impair downstream tissue remodeling.

How COX Enzyme Inhibition Shapes the Acute Tendon Environment

COX inhibition cascade mechanism diagram for tendon repair

When tendon tissue sustains mechanical trauma, phospholipase A2 releases arachidonic acid from cell membranes. Cyclooxygenase enzymes, specifically COX-1 and COX-2, convert that substrate into prostaglandins and thromboxanes. Prostaglandin E2 (PGE2), the dominant local mediator, sensitizes nociceptors (explaining post-injury pain) and recruits neutrophils and macrophages to the wound site.

Ketorolac inhibits both COX isoforms nonselectively, which:

  • Lowers PGE2 concentration in peritendinous fluid
  • Reduces lysosomal enzyme release from infiltrating neutrophils
  • Inhibits thromboxane-mediated platelet aggregation
  • Blunts nociceptor sensitization, producing rapid analgesia

"Ketorolac's analgesic effect in the acute phase is explicitly attributable to reduced prostaglandin levels, not to any direct structural action on tendon tissue."

This is an important distinction. Ketorolac is classified as an analgesic and short-term anti-inflammatory agent, not a tendon-healing drug. Drug-information resources updated in 2026 reinforce that its use is intended for brief durations because prolonged COX inhibition carries risks of gastrointestinal bleeding, renal toxicity, and interaction with other NSAIDs such as ibuprofen and naproxen.

The unresolved question is whether blunting PGE2 during days 1-4, precisely when the initial vascular, cellular, and matrix repair signals are being set, undermines the downstream remodeling that depends on controlled prostaglandin activity.


BPC-157 Healing Signaling: Growth Factor Up-Regulation vs. Prostaglandin Suppression

Ketorolac COX suppression versus BPC-157 healing signaling split comparison

Body Protection Compound 157 (BPC-157) is a 15-amino-acid synthetic peptide derived from a gastric protein. Its mechanism in tendon tissue is fundamentally different from NSAID pharmacology. Rather than blocking an enzyme, BPC-157 activates multiple anabolic and pro-repair signaling axes simultaneously.

Fibroblast Activation and FAK-Paxillin Signaling

Mechanistic work on tendon fibroblasts demonstrates that BPC-157:

  1. Accelerates outgrowth of tendon explants in culture
  2. Increases fibroblast migration and cell spreading
  3. Induces F-actin cytoskeletal reorganization
  4. Activates the focal adhesion kinase (FAK), paxillin pathway, a key integrin-associated signal that governs cell attachment and migration
  5. Enhances cell survival under oxidative stress conditions

This cytoskeletal and adhesion signaling is entirely upstream of COX enzymes. BPC-157 does not inhibit prostaglandins; it drives the structural machinery that fibroblasts need to synthesize and align new collagen.

Angiogenesis and VEGF-Linked Pathways

Tendons are hypovascular tissues. Adequate blood supply during the acute and subacute phases is critical for delivering oxygen, nutrients, and progenitor cells. BPC-157 up-regulates vascular endothelial growth factor (VEGF) and promotes neovascularization, an effect measured by neovascular indices in rat Achilles tendon-to-bone transection models. This contrasts with ketorolac's thromboxane inhibition, which moderately reduces platelet-driven angiogenic signaling.

Cytokine Modulation and Collagen Remodeling

A 2026 orthopaedic overview categorizes BPC-157 among experimental regenerative peptides that:

  • Down-regulate pro-inflammatory cytokines
  • Stimulate collagen synthesis and remodeling
  • Modulate the nitric oxide (NO) system, which is involved in both vascular tone and tendon cell biology

Researchers studying similar tissue-repair peptides have examined mitochondrial-targeted compounds like those reviewed in the SS-31 mechanism and research overview, which parallels BPC-157's cytoprotective profile in hypoxic or inflamed tissue environments.


Acute Phase Prostaglandin Modulation in Tendon Research: What the Data Show

Rat Achilles tendon histology slide with labeled repair zones

The phrase Ketorolac NSAID Suppression vs. BPC-157 Healing Signaling: Acute Phase Prostaglandin Modulation in Tendon Research describes a mechanistic tension rather than a head-to-head clinical trial, because no such trial currently exists.

What Rodent Models Reveal About BPC-157 in the Acute Phase

Early administration of BPC-157 (days 1-4) after rat Achilles tendon-to-bone transection produces measurable improvements in:

Outcome Measure Direction of Change with BPC-157
Achilles Functional Index Improved
Load to Failure Increased
Stiffness and Young's Modulus Increased
Collagen Organization Improved
Myeloperoxidase (MPO) Activity Decreased
Inflammatory Cell Influx Reduced
Neovascular Indices Increased

Notably, BPC-157 partially counteracts healing impairments caused by systemic corticosteroids, a different class of anti-inflammatory than NSAIDs, but one that also profoundly suppresses prostaglandin synthesis. This suggests BPC-157's pro-healing signaling can remain active even in a pharmacologically suppressed inflammatory environment.

Researchers interested in the broader landscape of peptides that support connective tissue recovery may also find value in reviewing resources on GHK-Cu copper peptide research and sourcing, as GHK-Cu shares some collagen-remodeling characteristics with BPC-157.

The Missing Data: NSAID-BPC-157 Tendon Co-administration

No published tendon study as of 2026 has directly examined ketorolac alongside BPC-157 during the acute phase to map prostaglandin suppression against growth factor up-regulation in the same model. The theoretical concern is straightforward:

  • Ketorolac eliminates PGE2, blunting neutrophil recruitment and early vascular signaling
  • BPC-157 drives FAK-paxillin activation and VEGF-mediated angiogenesis in the same window
  • Whether COX inhibition attenuates or is independent of BPC-157's receptor-level signals is unknown

Some researchers in sports medicine have begun exploring growth hormone secretagogue peptides, such as combinations studied in ipamorelin vs. tesa comparisons, as complementary tools for soft-tissue recovery, though these operate via entirely different hormonal axes than BPC-157.

Regulatory and Safety Context in 2026

Both the research optimism and the clinical caution around BPC-157 are well-founded. A 2025 narrative review explicitly warns that despite robust rodent data, no large human randomized controlled trials have been published, and unregulated off-label use in sports settings raises unresolved long-term safety concerns. The peptide holds no regulatory approval for tendon indications in any major jurisdiction as of 2026.

For researchers sourcing related experimental peptides for preclinical investigation, resources such as lab-tested peptide options provide guidance on quality standards relevant to research-grade compounds. Similarly, those examining mitochondrial and cytoprotective peptide mechanisms alongside tendon work may reference the MOTS-C and elamipretide research overview for comparative signaling context.


Conclusion

The contrast between ketorolac's COX-1/COX-2 enzyme inhibition and BPC-157's growth factor up-regulation represents one of the most conceptually significant gaps in acute tendon pharmacology. Ketorolac reliably reduces prostaglandins, lowers pain, and moderates early inflammatory cell trafficking, outcomes with real clinical value in the hours after injury. BPC-157, based on preclinical evidence, activates fibroblast FAK-paxillin signaling, VEGF-driven angiogenesis, and collagen remodeling during that same acute window.

Actionable next steps for researchers and clinicians:

  1. Design co-administration studies, preclinical models that administer both ketorolac and BPC-157 post-Achilles transection and measure functional, biomechanical, and histological outcomes at days 4, 14, and 28.
  2. Map prostaglandin levels explicitly, measure PGE2 and PGF2-alpha in peritendinous fluid in BPC-157-treated animals to determine whether the peptide itself modulates prostaglandin output or operates entirely through parallel pathways.
  3. Follow regulatory developments, monitor IND submissions and Phase I safety data for BPC-157 before considering any human application, as the evidence base does not yet support clinical use.
  4. Apply conservative NSAID dosing windows, until NSAID-BPC-157 tendon interaction data exist, clinicians should be cautious about prolonged COX inhibition during the critical days-1-to-4 repair window.

The field of regenerative tendon research in 2026 is at a crossroads between established pharmacology and promising but unvalidated peptide biology. Rigorous mechanistic studies examining Ketorolac NSAID Suppression vs. BPC-157 Healing Signaling: Acute Phase Prostaglandin Modulation in Tendon Research are the essential next step.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/ketorolac-nsaid-suppression-vs-bpc-157-healing-signaling-acute-phase-prostagland.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-29 13:19:092026-10-29 13:19:09Ketorolac NSAID Suppression vs. BPC-157 Healing Signaling: Acute Phase Prostaglandin Modulation in Tendon Research
Tizanidine vs. BPC-157 in Spasticity Models: Differentiating Muscle Tone Inhibition From Tissue Repair Signaling

Tizanidine vs. BPC-157 in Spasticity Models: Differentiating Muscle Tone Inhibition From Tissue Repair Signaling

October 28, 2026/0 Comments/in Uncategorized/by

Fewer than 40% of people living with spasticity from neurological conditions achieve adequate symptom control on a single agent, a persistent gap that has pushed researchers to explore peptide compounds alongside established antispasmodics. Understanding Tizanidine vs. BPC-157 in spasticity models: differentiating muscle tone inhibition from tissue repair signaling is not simply an academic exercise; it reflects two fundamentally different biological strategies that operate at separate points in the neuromuscular system.

Key Takeaways

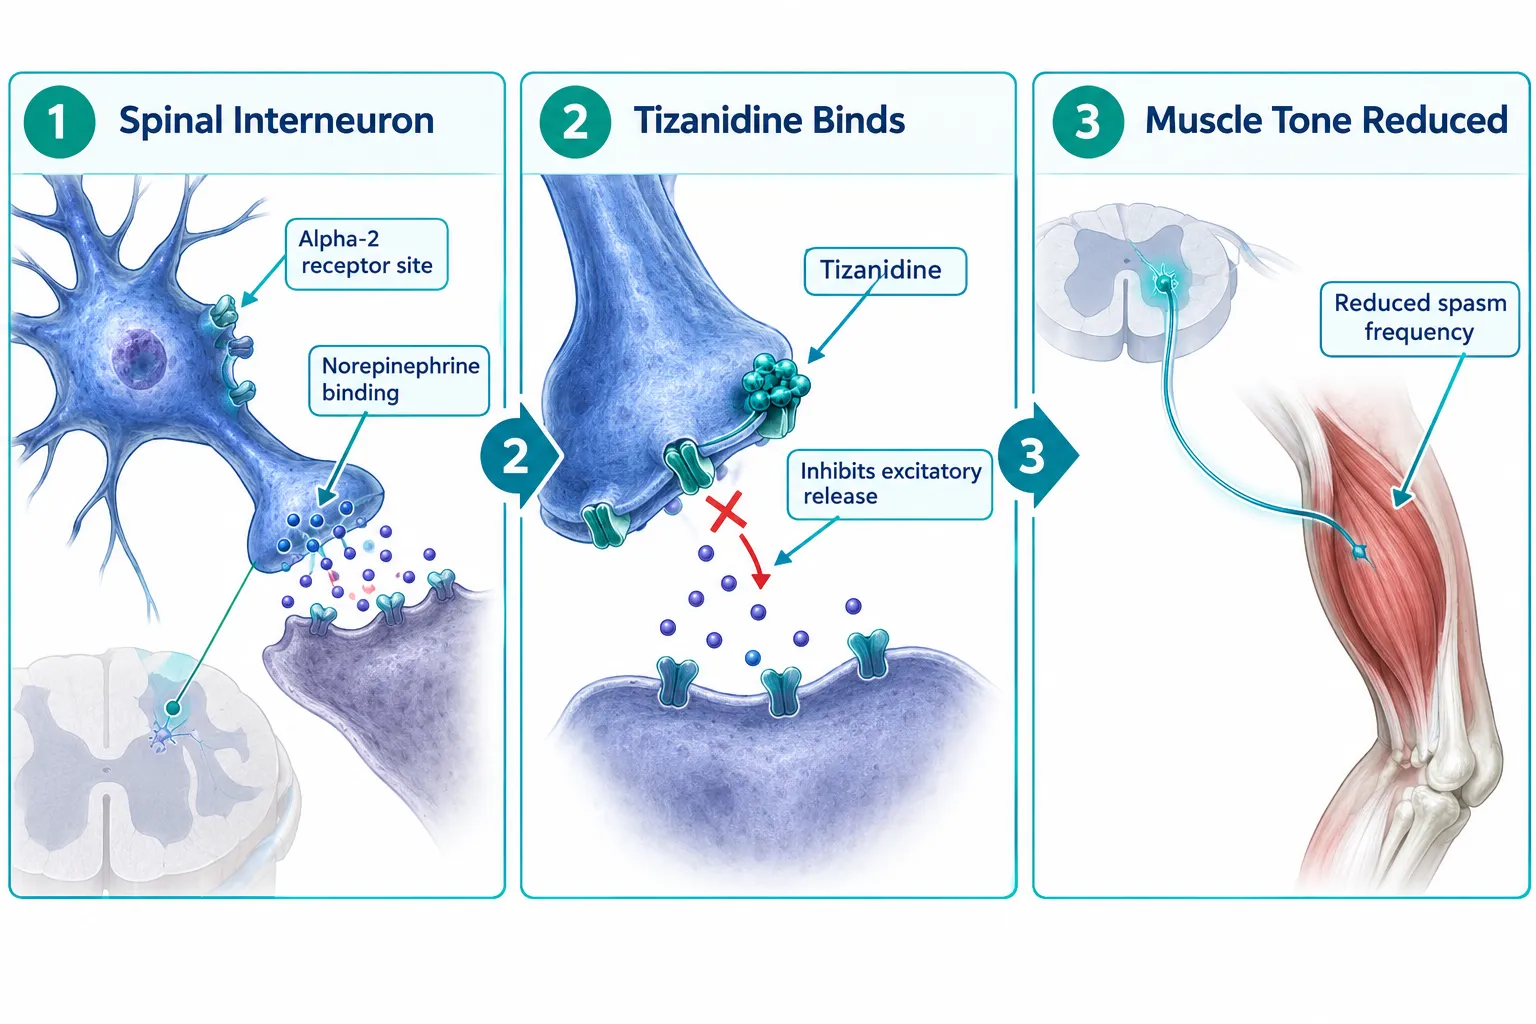
  • Tizanidine is an FDA-approved alpha-2 adrenergic agonist that reduces spasticity by suppressing excitatory motor neuron signaling in the spinal cord.
  • BPC-157 is a synthetic pentadecapeptide studied in preclinical models primarily for connective tissue repair, angiogenesis, and growth factor modulation, not spinal tone regulation.
  • No published head-to-head spasticity trial comparing tizanidine and BPC-157 exists as of late 2026.
  • The two compounds address different biological targets: central neural inhibition versus peripheral tissue remodeling.
  • Conflating antispasmodic action with tissue-repair peptide effects risks misapplication in both clinical and research contexts.

How Tizanidine Inhibits Muscle Tone

Tizanidine's pharmacological story begins in the dorsal horn of the spinal cord. As a centrally acting alpha-2 adrenergic agonist, it binds presynaptic receptors on spinal interneurons, suppressing the release of excitatory neurotransmitters, most notably glutamate and aspartate. The downstream result is a measurable reduction in polysynaptic reflex activity, which translates clinically to lower muscle tone and fewer involuntary spasms.

How Tizanidine Inhibits Muscle Tone

In controlled spasticity models, peak plasma concentrations occur within one to two hours of oral dosing, with antispasmodic effects detectable at doses as low as 2 mg. Clinical benchmarks show statistically significant reductions in Ashworth Scale scores at daily doses between 12 mg and 36 mg. Importantly, tizanidine's effect is duration-limited, it does not modify the underlying neurological lesion. When dosing stops, baseline tone typically returns within hours. This time-limited, reversible profile is characteristic of central muscle tone inhibition rather than any structural repair of muscle or connective tissue.

Key pharmacokinetic facts about tizanidine:

Parameter Value
Time to peak plasma level 1-2 hours
Half-life Approximately 2.5 hours
Primary mechanism Alpha-2 adrenergic agonism
Metabolism Hepatic (CYP1A2)
Approved indication Spasticity (MS, spinal cord injury)

Liver enzyme elevation is a clinically relevant concern with higher doses, making hepatic monitoring a standard practice in long-term users.


BPC-157 and Tissue Repair Signaling: A Different Biological Language

BPC-157, Body Protection Compound 157, is a synthetic 15-amino-acid peptide derived from a protein found in gastric juice. Its research profile sits firmly in the domain of tissue repair signaling rather than neurological tone modulation. Preclinical studies using rodent models of tendon laceration, ligament damage, and muscle contusion have documented upregulation of vascular endothelial growth factor (VEGF), enhanced collagen synthesis, accelerated fibroblast migration, and promotion of angiogenesis at injury sites.

BPC-157 and Tissue Repair Signaling: A Different Biological Language

These findings are mechanistically compelling. BPC-157 appears to interact with the nitric oxide system, modulate growth hormone receptor expression in locally damaged tissue, and influence the FAK-paxillin pathway involved in cell migration. For musculoskeletal injury assays, these effects translate to faster gross healing scores and improved tensile strength in repaired tendons.

However, none of these pathways directly reduce spinal cord-mediated motor neuron hyperexcitability. BPC-157 does not bind alpha-2 adrenergic receptors. It does not suppress glutamate release at spinal interneurons. Its peptide structure does not confer meaningful CNS penetration under standard dosing assumptions used in preclinical work.

Researchers studying peptide bioactivity can find a detailed breakdown of BPC-157's documented mechanisms in this BPC-157 core peptides documentation and first research guide. Those comparing peptide purity and supplier reliability for research applications should also consult peptide supplier comparisons interpreting PeptideTech and PeptidesC.

"BPC-157 speaks the language of wound repair. Tizanidine speaks the language of neural inhibition. Conflating the two is like comparing a structural engineer with an electrical engineer, both work on the same building, but through entirely separate systems."


Differentiating the Two in Spasticity Models: What the Evidence Actually Shows

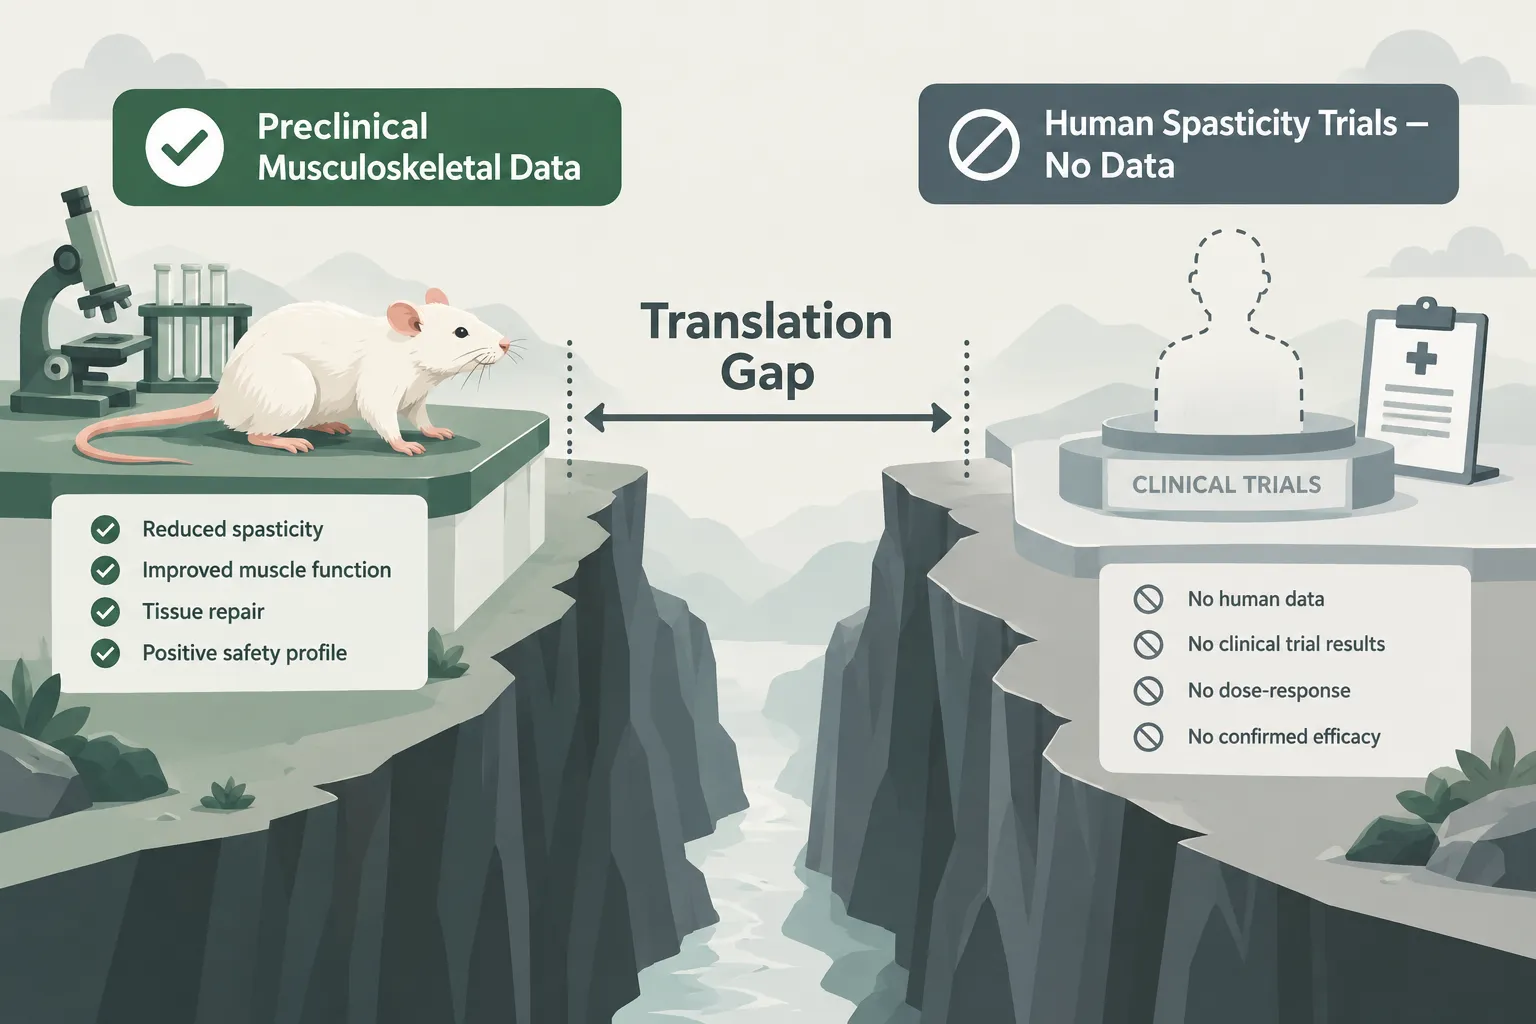
When evaluating Tizanidine vs. BPC-157 in spasticity models: differentiating muscle tone inhibition from tissue repair signaling, the most striking finding in the current literature is the near-complete absence of direct comparison data. As of late 2026, no peer-reviewed human trial has tested BPC-157 against a spasticity endpoint. Animal studies using BPC-157 have focused on muscle, tendon, and ligament injury, not upper motor neuron lesion models designed to replicate MS- or SCI-associated spasticity.

This creates an evidence asymmetry:

  • Tizanidine: Multiple randomized controlled trials, established dosing guidelines, inclusion in international spasticity management guidelines.
  • BPC-157: Robust preclinical musculoskeletal data, no regulatory approval for any indication in any major jurisdiction, no validated spasticity endpoint data in humans.

Differentiating the Two in Spasticity Models: What the Evidence Actually Shows

This does not mean BPC-157 has no role in musculoskeletal research. Investigators exploring peptide-assisted recovery after muscle damage, particularly secondary muscle changes that can accompany chronic spasticity, may find the compound's tissue-repair profile worth studying. Secondary muscle fibrosis and tendon dysfunction are real consequences of long-term spastic states, and repair signaling could theoretically address them. But that is a different research question from reducing neural tone.

Researchers interested in how peptide signaling intersects with systemic repair pathways can also review work on mitochondrial-targeted peptides such as SS-31, detailed in SS-31 mitochondrial research themes, or explore dosing considerations for peptides like SS-31 ideal dosage and timing. For those studying adjacent neuroendocrine pathways, MOTS-C and elamipretide offers insight into peptide-mediated cellular energy signaling. Labs sourcing compounds for controlled studies should review lab tested peptides to ensure research-grade purity standards are met.

Summary of mechanistic differences:

  • Target tissue: Tizanidine, spinal cord interneurons. BPC-157, peripheral connective tissue and vasculature.
  • Biological outcome: Tizanidine, reduced excitatory neurotransmission. BPC-157, enhanced angiogenesis and collagen remodeling.
  • Reversibility: Tizanidine, fully reversible on discontinuation. BPC-157, structural tissue changes may be durable.
  • Human evidence in spasticity: Tizanidine, strong. BPC-157, none currently available.

Expert commentary entering 2026 has flagged the regulatory uncertainty surrounding BPC-157, with several advisory bodies noting the need for formal phase I/II trial data before clinical integration can be responsibly recommended.


Conclusion

Tizanidine vs. BPC-157 in spasticity models: differentiating muscle tone inhibition from tissue repair signaling is ultimately a story about mechanistic clarity. Tizanidine has a well-defined, centrally mediated antispasmodic action backed by decades of controlled clinical data. BPC-157 operates through growth factor modulation and connective tissue remodeling pathways that are genuinely promising in injury-repair contexts but remain unvalidated for spasticity as a primary endpoint.

Actionable next steps for researchers and clinicians:

  1. Apply tizanidine within its validated indication, central spasticity management, using established dosing protocols and hepatic monitoring.
  2. Treat BPC-157 as a preclinical tissue-repair compound, not an antispasmodic substitute, until human spasticity trial data emerge.
  3. When designing research protocols comparing neuromodulatory agents with peptide-based compounds, ensure model selection reflects the distinct biological targets of each agent.
  4. Monitor emerging literature for phase I human data on BPC-157, particularly in populations with secondary musculoskeletal complications of long-term spasticity.
  5. Confirm peptide research quality through verified, lab-tested sources before conducting any controlled study.

The two compounds are not competitors within the same mechanism, they are representatives of two distinct scientific traditions. Recognizing that distinction is the first step toward deploying each responsibly.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/tizanidine-vs-bpc-157-in-spasticity-models-differentiating-muscle-tone-inhibitio.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-28 13:04:292026-10-28 13:04:29Tizanidine vs. BPC-157 in Spasticity Models: Differentiating Muscle Tone Inhibition From Tissue Repair Signaling
Pregabalin Confounding Factors in BPC-157 Neuropathic Pain Models: Controlling Central vs. Peripheral Signaling

Pregabalin Confounding Factors in BPC-157 Neuropathic Pain Models: Controlling Central vs. Peripheral Signaling

October 27, 2026/0 Comments/in Uncategorized/by

Fewer than a handful of peer-reviewed studies have tested BPC-157 and a gabapentinoid in the same neuropathic pain model, yet pregabalin remains one of the most commonly prescribed background treatments in patients and animals used in chronic pain research. That gap is a serious methodological problem. When pregabalin confounding factors in BPC-157 neuropathic pain models go unaddressed, researchers risk misattributing centrally driven analgesia to a peptide whose primary actions appear to be peripheral and reparative.

Key Takeaways

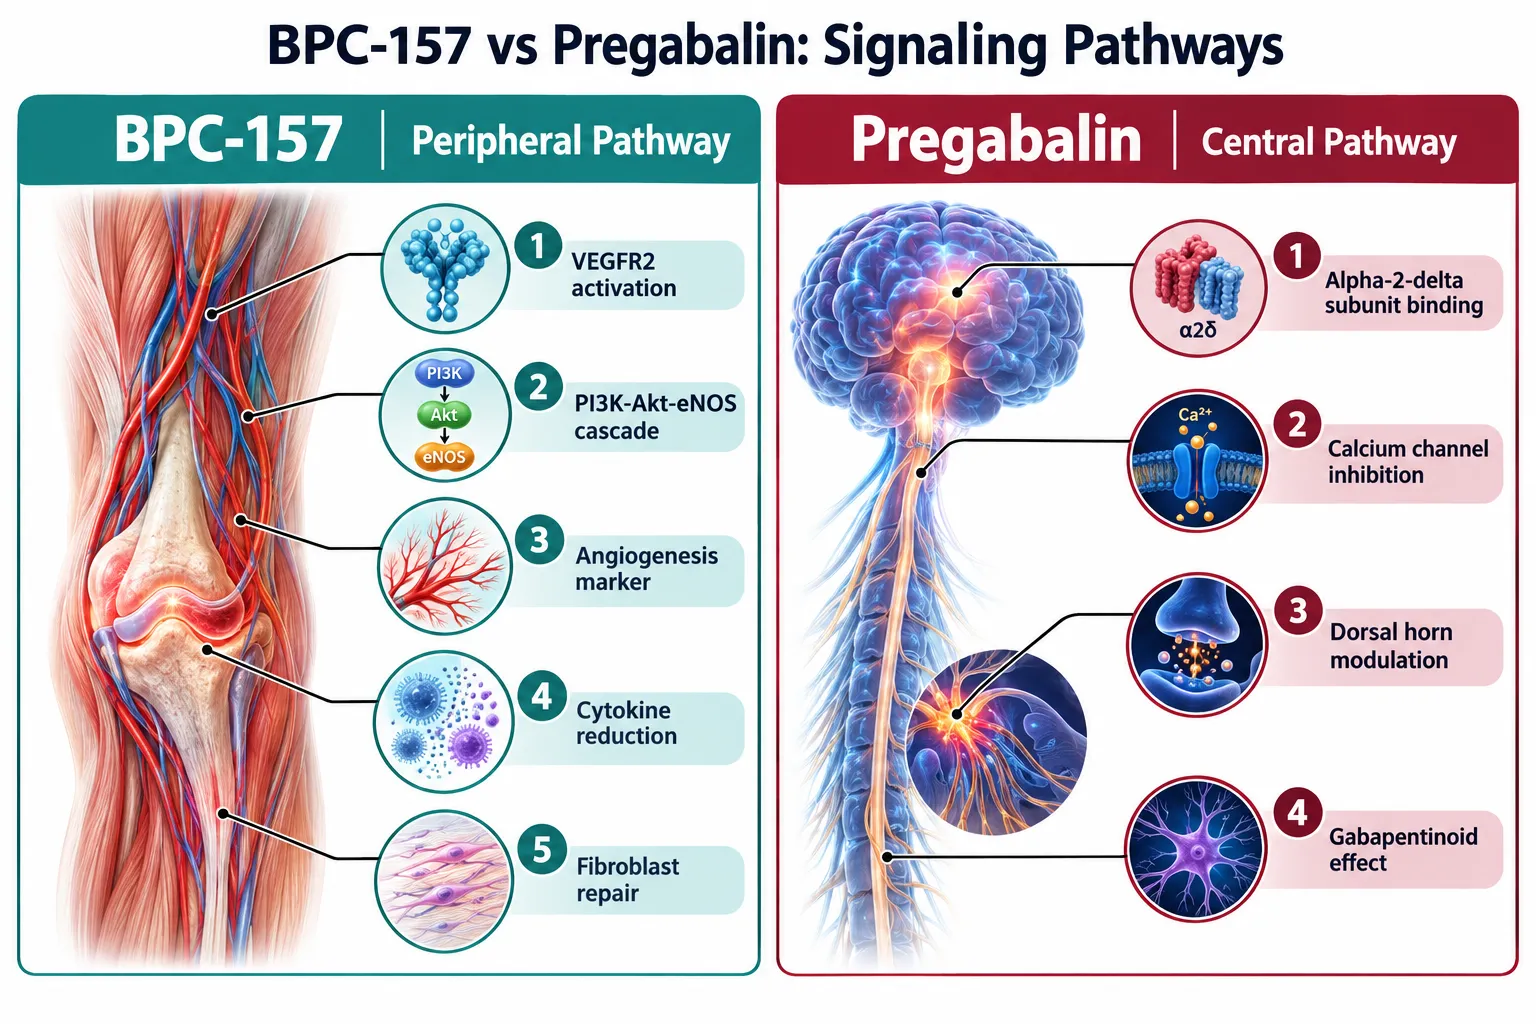
  • BPC-157 exerts its analgesic and reparative effects largely through peripheral pathways, VEGFR2, PI3K-Akt-eNOS, and cytokine reduction, rather than through classic central neuromodulation.
  • Pregabalin suppresses neuropathic pain by binding alpha-2-delta calcium channel subunits in the spinal cord and brain, a mechanism that can mask or mimic BPC-157's behavioral pain outcomes.
  • No published protocol currently mandates pregabalin washout before BPC-157 administration in neuropathic pain assays, creating an uncontrolled variable in polypharmacy settings.
  • Controlling central vs. peripheral signaling requires pairing behavioral tests with peripheral biomarkers such as cytokine profiles, oxidative stress indices, and angiogenesis markers.
  • Standardized exclusion or stratification of gabapentinoid use is the single most actionable step researchers can take to improve mechanistic clarity in future BPC-157 trials.

Why the BPC-157 Signaling Profile Matters

Why the BPC-157 Signaling Profile Matters

BPC-157 is a synthetic pentadecapeptide derived from a gastric protein. Across a wide range of preclinical models, nerve crush, ischemia-reperfusion, musculoskeletal injury, it consistently reduces inflammatory cytokines, improves microvascular integrity, and accelerates tissue repair. Its primary molecular targets include the VEGFR2-PI3K-Akt-eNOS axis and ERK1/2 pathways, both of which drive angiogenesis, fibroblast activity, and neuromuscular stabilization.

Crucially, the antinociceptive effects documented in these models appear to be largely anti-inflammatory and short-lived rather than the sustained central analgesia associated with classical pain drugs. Some preclinical data do show BPC-157 interacting with opioid and dopaminergic systems, suggesting a modest central component, but this remains poorly characterized. The peptide also shows a strong interaction with the nitric oxide (NO) system and can modulate morphine-induced analgesia, a finding that complicates any co-administration design.

Key peripheral biomarkers used to track BPC-157 effects include:

Biomarker Category Relevance
IL-6 immunoreactivity Inflammatory Reduced by BPC-157 in nerve and brain injury
MDA (malondialdehyde) Oxidative stress Lowered in ischemia-reperfusion models
SOD activity Antioxidant defense Restored after BPC-157 treatment
VEGF expression Angiogenesis Partially upregulated by BPC-157
Bax / Caspase-3 Apoptosis Down-regulated in neural tissue

Researchers using only behavioral pain endpoints, paw withdrawal threshold, von Frey filaments, without these peripheral markers cannot distinguish whether observed improvements come from BPC-157's tissue-level repair or from a co-administered gabapentinoid suppressing spinal transmission.


Understanding Pregabalin Confounding Factors in BPC-157 Neuropathic Pain Models

Understanding Pregabalin Confounding Factors in BPC-157 Neuropathic Pain Models

Pregabalin binds to the alpha-2-delta subunit of voltage-gated calcium channels throughout the central nervous system, reducing the release of excitatory neurotransmitters in the dorsal horn and supraspinal pain centers. This mechanism is entirely central, it does not repair peripheral nerve tissue, reduce cytokines at the injury site, or promote angiogenesis.

The confounding problem arises because behavioral pain tests measure the endpoint, not the mechanism. A rat that receives both BPC-157 and pregabalin will show reduced mechanical allodynia, but that reduction could reflect:

  • Central calcium channel suppression from pregabalin alone
  • Peripheral anti-inflammatory repair from BPC-157 alone
  • An additive or synergistic interaction between both
  • An antagonistic interaction canceling one agent's effect

Without pregabalin washout or a rigorous vehicle-control group, none of these scenarios can be separated.

"Attributing outcome changes to BPC-157 in any polypharmacy setting requires, at minimum, stratification or controlled exclusion of background gabapentinoid use."

This issue is amplified by the fact that gabapentinoids are standard-of-care comparators in many neuropathic pain protocols. Researchers testing BPC-157 against a pregabalin comparator arm sometimes fail to include a drug-free BPC-157 arm, making it impossible to know whether the peptide has independent analgesic activity or simply adds noise to a pregabalin-dominant effect.

Three scenarios where pregabalin confounding factors in BPC-157 neuropathic pain models most commonly arise:

  1. Background polypharmacy, Animals or patients already receiving pregabalin when BPC-157 is introduced
  2. Positive-control design flaws, Pregabalin used as a comparator without a washout between phases
  3. Translation errors, Preclinical models that inherit clinical dosing conventions where gabapentinoids are always on board

Controlling Central vs. Peripheral Signaling: A Practical Framework

Controlling Central vs. Peripheral Signaling: A Practical Framework

Controlling central vs. peripheral signaling in BPC-157 research requires more than removing pregabalin from the protocol. It demands a multi-layer experimental design that produces mechanistic evidence alongside behavioral data.

Recommended protocol elements:

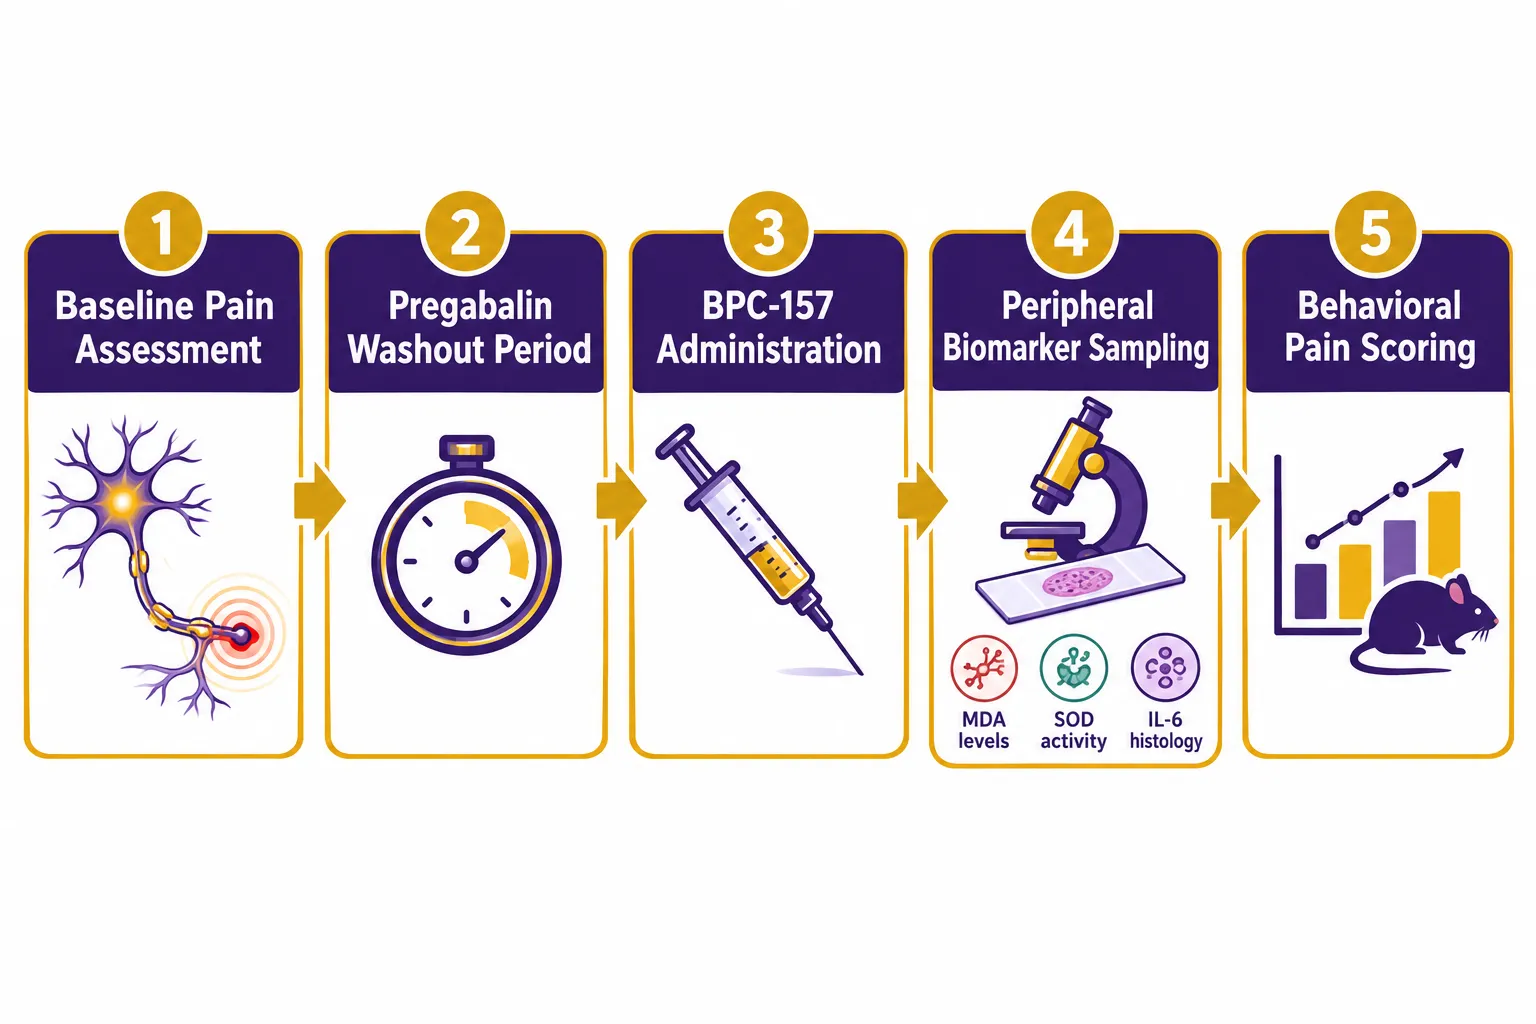
  • Pregabalin washout period of at least five half-lives before BPC-157 dosing begins, documented in the methods section
  • Peripheral biomarker panel including cytokines, oxidative stress indices (MDA, SOD), and histological angiogenesis markers collected alongside behavioral tests
  • Sham-surgery and vehicle arms that match every drug group for injection stress and handling
  • Dose-response design for BPC-157 independent of any gabapentinoid, establishing its intrinsic analgesic ceiling
  • Blinded behavioral assessment to prevent observer bias when groups receive different pharmacological profiles

Researchers interested in how structural peptides modulate systemic repair responses, similar in some ways to the cytoprotective profiles seen with SS-31 peptides, should apply the same rigor: isolate the peptide's contribution before adding co-interventions.

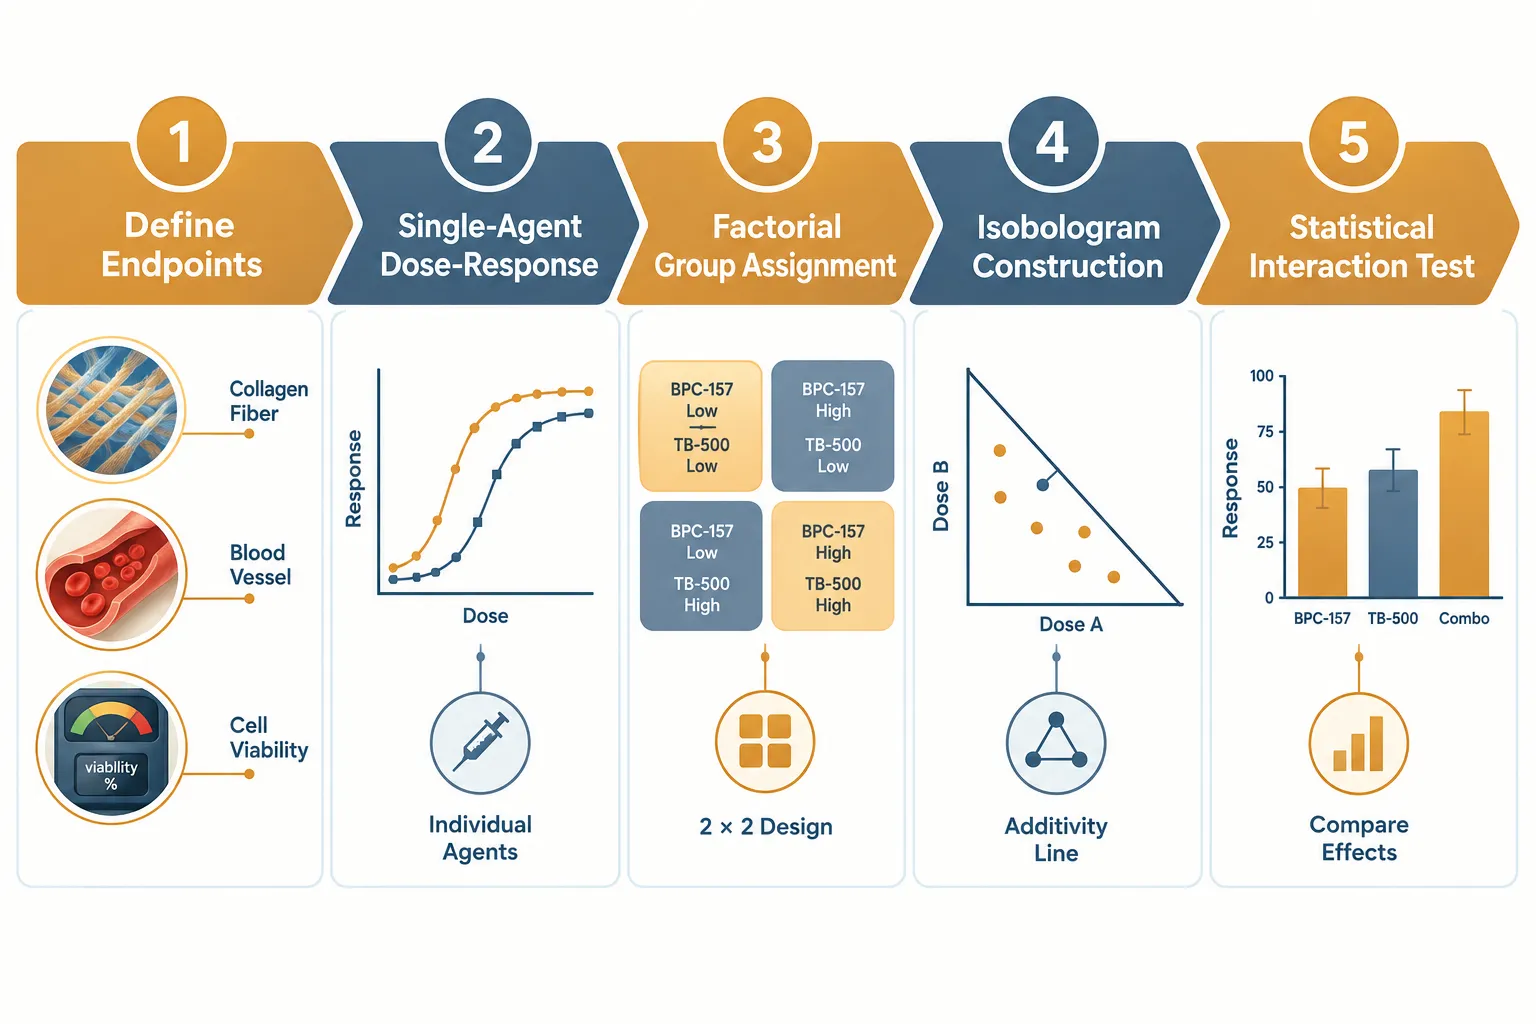
When combination studies are unavoidable, a factorial design (BPC-157 alone, pregabalin alone, both combined, vehicle control) allows statistical separation of each agent's contribution. This design is standard in pharmacology but is rarely applied to BPC-157 research, which currently lacks any randomized controlled trial in neuropathic pain.

The interaction between BPC-157 and the NO system is another variable requiring control. Because pregabalin does not directly modulate NO signaling, any difference in NO-pathway biomarkers between groups can serve as a partial internal control, but only if those markers are measured. Parallel peptide research, such as work with SS31 and MOTS-C combinations, has modeled how to separate mitochondrial from vascular endpoints in the same assay, a useful methodological template.

What the current evidence does and does not support:

  • SUPPORTED: BPC-157 reduces peripheral inflammatory markers and promotes vascular repair in preclinical models
  • SUPPORTED: Pregabalin provides central analgesia through a distinct, well-defined mechanism
  • NOT YET ESTABLISHED: Whether BPC-157 provides independent neuropathic analgesia when gabapentinoids are excluded
  • NOT YET ESTABLISHED: Whether combining BPC-157 and pregabalin is synergistic, additive, or neutral

The absence of human randomized trials in neuropathic pain means that clinical translation of any BPC-157 analgesic claim remains premature, particularly when gabapentinoid use has not been controlled. Small pilot studies in musculoskeletal pain and interstitial cystitis report potential benefit, but none rigorously excluded or stratified pregabalin use.


Conclusion

Pregabalin confounding factors in BPC-157 neuropathic pain models represent one of the most tractable but underaddressed problems in current peptide pain research. The solution is not exotic, it requires standard pharmacological controls that are already well-established in drug development.

Actionable next steps for researchers:

  1. Audit existing protocols for concurrent gabapentinoid use and document it explicitly, even in retrospective analyses.
  2. Mandate peripheral biomarker collection alongside every behavioral pain endpoint to separate tissue-level repair from central symptom suppression.
  3. Adopt factorial designs when combination studies are necessary, ensuring BPC-157's independent effect can be statistically isolated.
  4. Establish pregabalin washout standards specific to the animal model and publish them as part of the methods so replication is possible.
  5. Pre-register future neuropathic pain trials with explicit gabapentinoid exclusion or stratification criteria to improve mechanistic clarity and regulatory credibility.

Controlling central vs. peripheral signaling is not a minor methodological footnote, it is the difference between discovering a genuinely peripheral neuroregenerative agent and producing ambiguous data that cannot guide clinical use.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/pregabalin-confounding-factors-in-bpc-157-neuropathic-pain-models-controlling-ce.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-27 13:10:162026-10-27 13:10:16Pregabalin Confounding Factors in BPC-157 Neuropathic Pain Models: Controlling Central vs. Peripheral Signaling
Klow Peptide Nasal Spray vs Single-Agent Semax or Selank: Designing a Formulation-First Comparison

Klow Peptide Nasal Spray vs Single-Agent Semax or Selank: Designing a Formulation-First Comparison

October 26, 2026/0 Comments/in Uncategorized/by

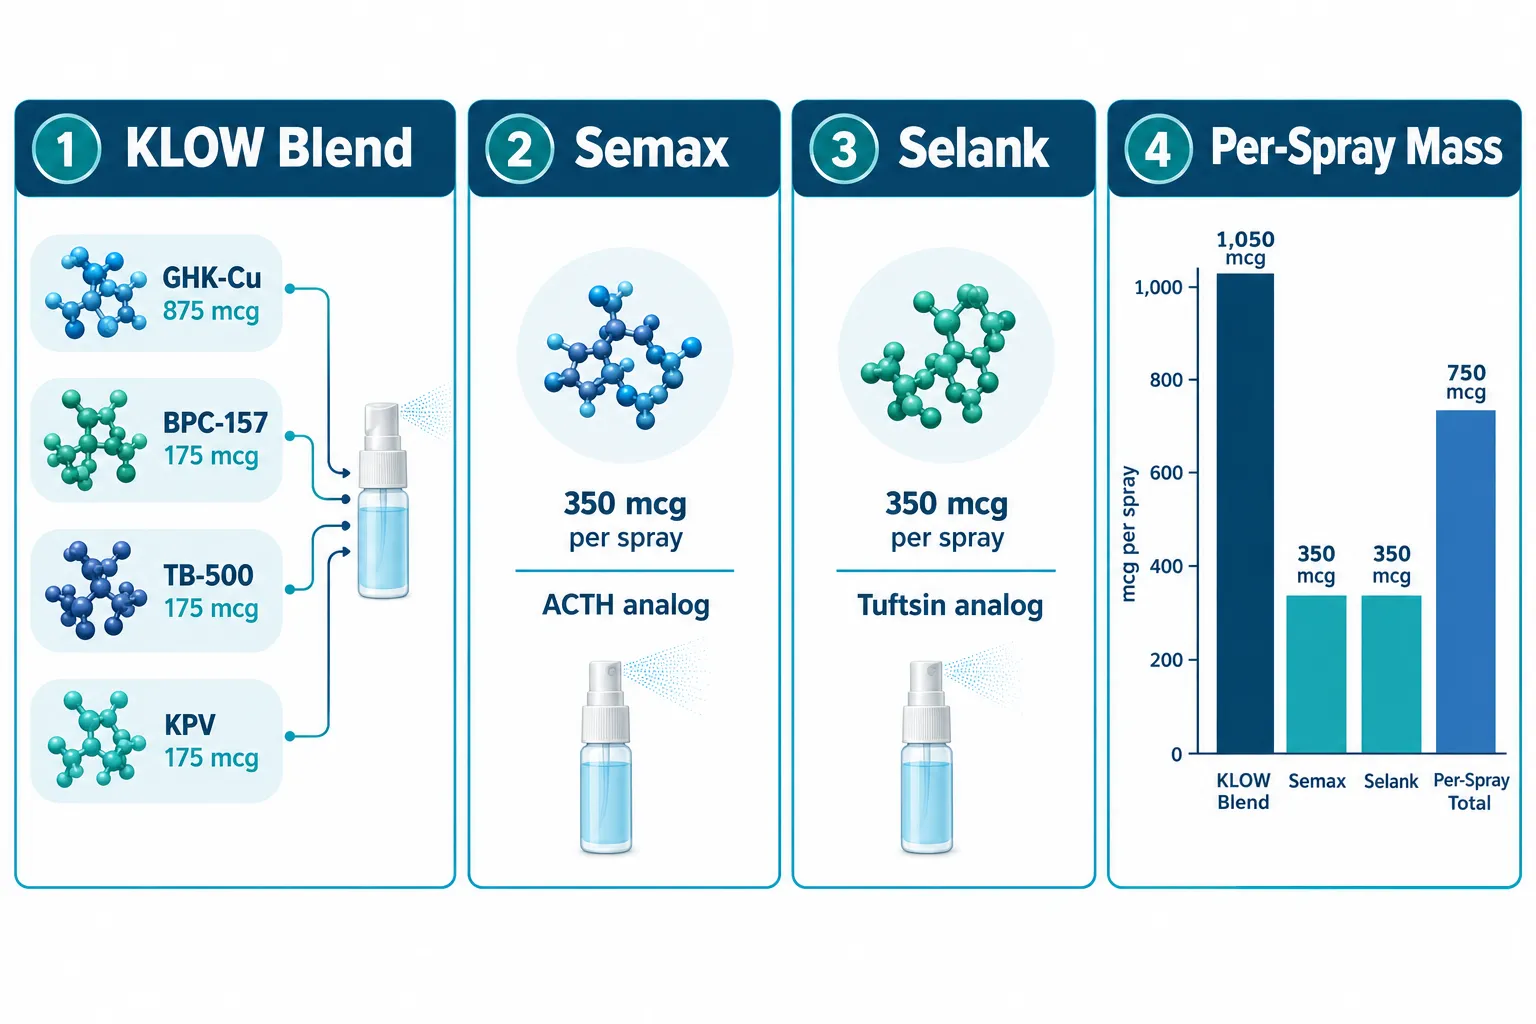
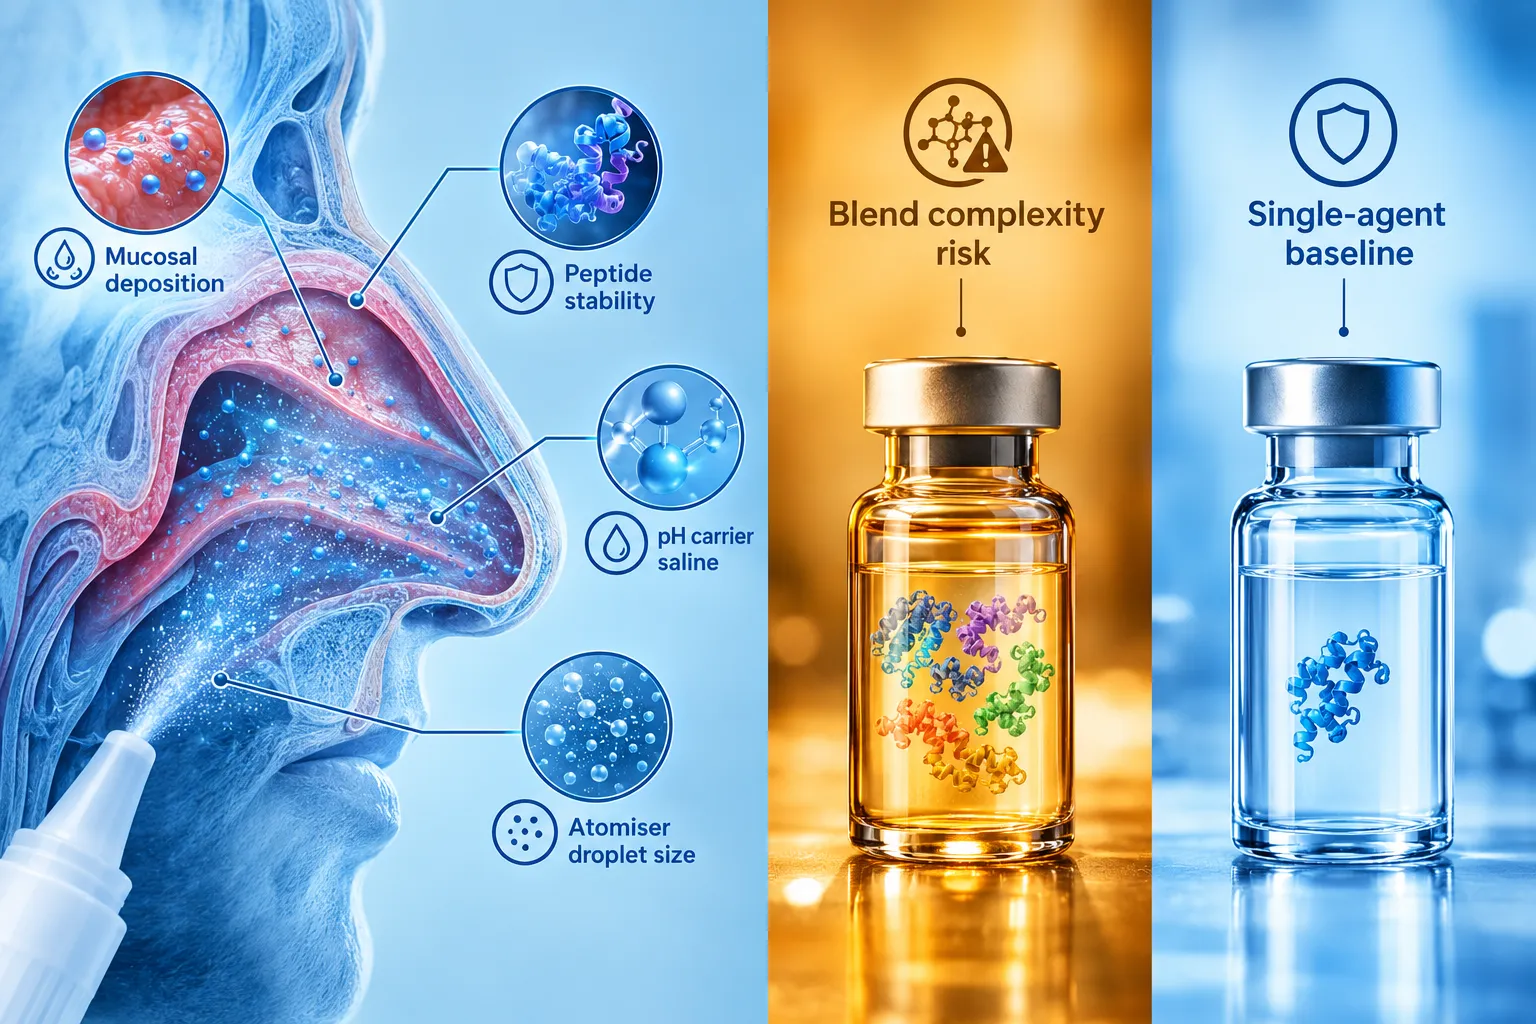
Roughly 80 mg of total peptide mass fits inside a single 10 mL nasal spray bottle, and whether that mass comes from one compound or four determines almost everything else about how researchers plan, dose, and interpret results. The Klow Peptide Nasal Spray vs Single-Agent Semax or Selank: Designing a Formulation-First Comparison is not, at its core, an efficacy debate. It is a formulation engineering question: blend complexity, excipient behavior, nasal deposition geometry, peptide stability, and the ability to attribute endpoints to a specific active ingredient.

Key Takeaways

  • KLOW nasal spray delivers four peptides (GHK-Cu, BPC-157, TB-500, KPV) at a combined 1.4 mg per spray, targeting skin and tissue-repair research pathways.
  • Single-agent Semax and Selank nasal sprays each deliver approximately 350 mcg per spray of one neuropeptide, used for cognitive and anxiolytic research respectively.
  • These two categories address fundamentally different tissue targets and research endpoints, making direct efficacy comparisons unsupported by current evidence.
  • Blend formulations increase total peptide mass per spray but complicate endpoint attribution when multiple active compounds are present simultaneously.
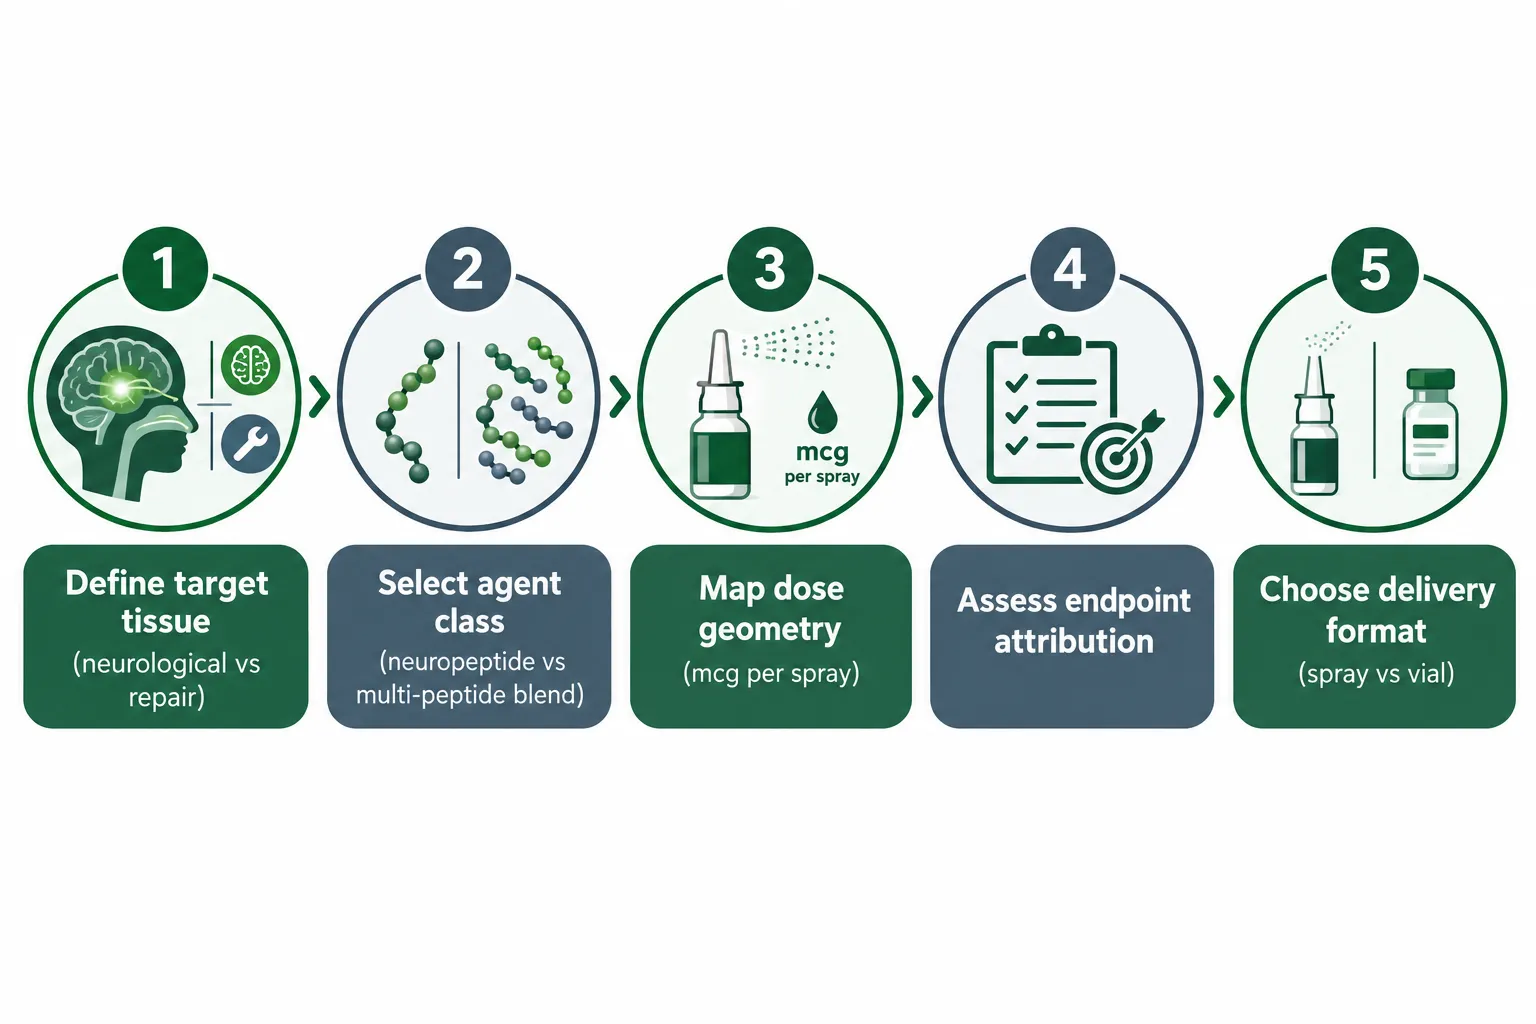
  • Formulation-first evaluation criteria, dose geometry, excipient choice, stability risk, and deposition, are more reliable comparison axes than unsupported efficacy rankings.

What KLOW Nasal Spray Actually Contains

KLOW nasal spray is described by Canadian suppliers as a ready-mixed, four-peptide intranasal research product. Each 10 mL bottle contains 50 mg GHK-Cu, 10 mg BPC-157, 10 mg TB-500, and 10 mg KPV, 80 mg total, dissolved in sterile saline and delivered through a metered atomiser. Each bottle yields approximately 57 sprays, and every actuation delivers roughly 1.4 mg of total peptide: 875 mcg GHK-Cu plus 175 mcg each of BPC-157, TB-500, and KPV.

KLOW is explicitly positioned as "GLOW plus KPV." GLOW is the three-peptide base (GHK-Cu, BPC-157, TB-500); KPV is an anti-inflammatory tripeptide added to address inflammatory pathway research. This modular design philosophy, building a tissue-repair base and layering in a targeted co-peptide, is a defining feature of the KLOW formulation approach.

For researchers already familiar with documentation-first peptide protocols, the approach mirrors the sourcing discipline described in resources like the BPC-157 core peptides documentation first research guide, where understanding what is inside a formulation before designing a protocol is treated as non-negotiable.

What KLOW Nasal Spray Actually Contains

How Single-Agent Semax and Selank Nasal Sprays Are Formulated

Semax nasal spray products are typically formatted as 10 mg in 5 mL or 20 mg in 10 mL, yielding 28 or 57 sprays respectively, with each spray delivering approximately 350 mcg of the single active neuropeptide. Selank follows the same volume-and-concentration pattern.

These are clean, single-mechanism formulations. Semax is a synthetic analog of ACTH 4-10, developed for attention, memory, neuroprotection, and stroke recovery research. Selank is a tuftsin analog, studied for anxiolytic effects and immune modulation. Both have a long history of intranasal use in Russia and are not FDA-approved. Published small-study data report outcomes such as up to 60% reductions in self-rated anxiety scores with Selank and 10-20% improvements in short-term memory with Semax at daily doses of 200-600 mcg delivered in 2-3 sprays.

The Semax peptide research category is distinct from tissue-repair peptide research. When a protocol uses Semax or Selank, the endpoint is neurological. When it uses KLOW, the endpoint is dermal, connective tissue, or systemic inflammatory in nature. These are different experiments.

How Single-Agent Semax and Selank Nasal Sprays Are Formulated

Formulation-First Criteria for Comparing Blend vs Single-Agent Sprays

A rigorous Klow Peptide Nasal Spray vs Single-Agent Semax or Selank: Designing a Formulation-First Comparison must address five technical dimensions before any research endpoint discussion.

Dose Geometry

Parameter KLOW (per spray) Semax or Selank (per spray)
Total peptide mass ~1.4 mg ~0.35 mg
Active compounds 4 1
GHK-Cu contribution 875 mcg None
Neuropeptide content None 350 mcg
Carrier Sterile saline Sterile saline

On a per-spray basis, KLOW delivers four times the total peptide mass of a Semax or Selank spray, but none of that mass is a neuropeptide. The mass comparison is not interchangeable, it measures different molecules hitting different receptor classes.

Endpoint Attribution

Multi-peptide blends create an attribution problem. If a researcher observes a change in a measurable marker after using KLOW, it is not straightforward to assign that change to GHK-Cu, BPC-157, TB-500, or KPV individually. Single-agent Semax or Selank protocols avoid this entirely: one peptide, one primary mechanism, one cleaner causal chain.

No clinical trial has directly compared Semax and Selank against each other for any outcome, let alone against a four-peptide tissue-repair blend. Accordingly, any formulation-first comparison must hold its conclusions to molecular class, dosing geometry, and target tissue, not to efficacy rankings.

Stability and Excipient Effects

Four peptides dissolved together in a single saline solution introduce more complexity than a single-peptide solution does. Potential peptide-peptide interactions, differential degradation rates, and pH sensitivity across compounds all raise stability questions that single-agent solutions sidestep. Sterile saline is a neutral, low-risk excipient for all five compounds under discussion, but blend stability should be verified through lab tested peptides documentation before any research protocol begins.

Nasal Deposition

Metered nasal atomisers produce consistent droplet sizes and spray geometry regardless of which peptides they carry. Both KLOW and single-agent sprays use sealed metered pump systems, eliminating reconstitution steps and bacteriostatic water variables. The key delivery difference is that KLOW's higher total mass per actuation means more peptide contacts the mucosal surface per spray, but whether that translates into proportionally higher absorption depends on tissue saturation and mucociliary clearance rates, not formulation design alone.

Research Use-Case Categorization

Supplier catalogs consistently place KLOW under skin, tissue repair, and inflammation research and Semax/Selank under cognitive, neuroprotection, stress, and anxiety research. This is the clearest practical guidance available for choosing between these formulation strategies: define the research question first, then select the peptide class that addresses that tissue target.

Research Use-Case Categorization

Designing a Comparison Protocol

When designing a Klow Peptide Nasal Spray vs Single-Agent Semax or Selank: Designing a Formulation-First Comparison protocol for research purposes, the following steps apply:

  1. Define the target tissue, neurological versus dermal/connective tissue.
  2. Select the agent class, neuropeptide (Semax, Selank) or tissue-repair blend (KLOW).
  3. Map dose geometry, document mcg per spray, sprays per session, and daily total peptide exposure.
  4. Plan endpoint attribution, single-agent designs support cleaner causal inference.
  5. Verify formulation standards, confirm sterility, metered delivery, and stability data from the supplier.

For researchers tracking broader peptide nasal spray ecosystems, vendor catalogs in 2026 now include single-agent BPC-157, TB-500, GHK-Cu, KPV, NAD+, oxytocin, and multi-peptide blends alongside Semax, Selank, and combination Semax+Selank sprays. This expansion reflects a shift toward configurable intranasal platforms rather than isolated single-agent solutions, a trend that makes formulation-first thinking increasingly important.

Resources on adjacent peptide classes, such as tesa peptide benefits, illustrate how single-agent peptide research maintains cleaner mechanistic interpretability, a standard worth applying across any nasal spray comparison.


Conclusion

The comparison between KLOW nasal spray and single-agent Semax or Selank is fundamentally a formulation design question, not a performance contest. KLOW packs four tissue-repair peptides into 1.4 mg per spray; Semax and Selank each deliver 350 mcg of a single neuropeptide per spray. They target different tissues, serve different research endpoints, and create different attribution challenges when outcomes are measured.

Actionable next steps for researchers:

  • Start with a clearly defined target tissue and endpoint before selecting any nasal spray format.
  • Use single-agent Semax or Selank when causal clarity matters and the research focus is neurological or anxiolytic.
  • Use KLOW when the research question spans tissue repair, skin biology, and inflammation simultaneously, and document all four components in the protocol.
  • Verify formulation quality through third-party tested sources and confirm metered pump specifications before beginning any dosing schedule.
  • Treat blend complexity as a variable to control for, not a proxy for potency.

Formulation-first thinking protects research integrity and keeps interpretation grounded in what is actually known about each peptide class.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/klow-peptide-nasal-spray-vs-single-agent-semax-or-selank-designing-a-formulation.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-26 13:05:152026-10-26 13:05:15Klow Peptide Nasal Spray vs Single-Agent Semax or Selank: Designing a Formulation-First Comparison
GHK-Cu and Glow Blend in Keratinocyte Models: Separating Copper Signaling From Multi-Peptide Formulation Effects

GHK-Cu and Glow Blend in Keratinocyte Models: Separating Copper Signaling From Multi-Peptide Formulation Effects

October 23, 2026/0 Comments/in Uncategorized/by

Keratinocytes make up roughly 90 percent of the human epidermis, yet most peptide research in dermal biology focuses on fibroblasts. That oversight matters when evaluating GHK-Cu and Glow Blend in keratinocyte models: separating copper signaling from multi-peptide formulation effects requires a different set of assays, different readouts, and a much stricter eye for what the data actually prove.

The Glow Blend is a three-peptide research formulation containing GHK-Cu 50 mg, BPC-157 10 mg, and TB-500 10 mg in a single 70 mg vial. Each component carries its own mechanistic story, but no published study has yet tested all three together in a controlled keratinocyte model. Understanding what is known, and what is being extrapolated, is essential before drawing any conclusions about the blend's epidermal effects.

Key Takeaways

  • GHK-Cu has the strongest keratinocyte-specific evidence, including biopsy-confirmed proliferation data and at least one small randomized controlled trial in humans.
  • The Glow Blend (GHK-Cu 50 mg, BPC-157 10 mg, TB-500 10 mg) has no published multi-peptide keratinocyte study; all blend claims are extrapolated from single-peptide data.
  • Copper signaling through GHK-Cu drives Nrf2 nuclear translocation, antioxidant response element gene expression, and barrier protein production in epidermal keratinocyte assays.
  • BPC-157 and TB-500 primarily target vascularization and actin-mediated migration respectively, pathways that are secondary rather than primary in keratinocyte monolayer models.
  • Research suppliers explicitly frame the Glow Blend as a hypothesis-generating tool for studying pathway complementarity, not as a validated synergistic protocol.

How Copper Signaling Works in Keratinocyte Assays

How Copper Signaling Works in Keratinocyte Assays

GHK-Cu (glycyl-L-histidyl-L-lysine copper complex) is the dominant copper-signaling agent in the Glow Blend, and keratinocyte assays are where its evidence base is most clearly defined. In human epidermal keratinocyte (HEK) monolayer cultures and wound-healing scratch assays, GHK-Cu has been shown to modulate the expression of thousands of genes, stimulating type I and type III collagen, elastin, and glycosaminoglycan production. More relevant to the epidermis specifically, biopsy data from a study of 67 women aged 50 to 59 using a GHK-Cu cream showed strong keratinocyte proliferation alongside improvements in laxity, clarity, and firmness.

The mechanistic pathway most studied in keratinocyte-specific models involves Nrf2 nuclear translocation and activation of antioxidant response element (ARE) gene expression. Standard HEK cultures and scratch-assay protocols allow researchers to quantify:

  • Migration rate, how fast keratinocytes close a defined wound gap
  • Oxidative stress markers, reactive oxygen species levels before and after copper complex exposure
  • Barrier protein expression, genes associated with tight junction and cornified envelope integrity
  • Proliferation index, cell count and division rate as direct readouts of copper-driven signaling

This set of readouts is distinct from the fibroblast-matrix assays that dominate most GHK-Cu literature. Separating these epidermal endpoints from fibroblast collagen endpoints is central to understanding what "copper signaling" actually does at the skin's outermost functional layer.

A 2024 study on GHK-Cu-functionalized silver nanoparticles also reported accelerated re-epithelialization and preserved keratinocyte viability in a rat full-thickness wound model, adding further support for copper-mediated repair signaling that operates independently of any multi-peptide blend. Researchers sourcing materials for these models should review the GHK-Cu peptide purchase and copper peptide research sourcing guide before designing experiments.


Parsing Each Peptide's Role: What the Glow Blend Components Do in Epidermal Models

Parsing Each Peptide's Role: What the Glow Blend Components Do in Epidermal Models

When evaluating GHK-Cu and Glow Blend in keratinocyte models: separating copper signaling from multi-peptide formulation effects depends on understanding where BPC-157 and TB-500 fit, and where they do not, in the epidermal context.

GHK-Cu functions primarily as an extracellular matrix remodeler and gene expression driver. In keratinocyte-rich models, its copper-dependent activity governs ECM remodeling and barrier gene upregulation.

BPC-157 promotes angiogenesis through VEGF and eNOS signaling pathways and drives new dermal capillary formation. These effects are more relevant to the dermis and subdermal tissue than to the epidermis itself. Keratinocyte monolayers, which lack vasculature, will show limited response to BPC-157's primary mechanism. For context on BPC-157 documentation standards in preclinical work, the BPC-157 core peptides documentation and first research guide provides a useful framework.

TB-500, the thymosin β4 fragment, regulates G/F-actin dynamics and drives keratinocyte, endothelial, and fibroblast migration. This is one area where TB-500 does have direct keratinocyte relevance: actin polymerization is central to scratch-assay closure. However, when BPC-157 and TB-500 were combined in a 2026 rat Achilles-tendon model, the combination did not outperform either peptide alone, a result that should temper assumptions about synergy in any multi-peptide context.

Research note: The Glow Blend’s three components are described as targeting “non-overlapping repair pathways”, but non-overlapping does not automatically mean additive. In keratinocyte models, pathway complementarity must be measured, not assumed.
Peptide Primary Mechanism Keratinocyte Relevance
GHK-Cu ECM remodeling, Nrf2/ARE gene expression High, direct proliferation and barrier data
BPC-157 VEGF/eNOS angiogenesis Low-to-moderate, no vasculature in monolayer
TB-500 G/F-actin dynamics, migration Moderate, scratch-assay closure readouts

Protocols seeking to isolate GHK-Cu's keratinocyte effects should run single-peptide controls before testing any blend. Researchers can also review comparable quality-control workflows in the TB-500 buy controlled experimental models and QC workflow resource.


Evidence Gaps and the Preclinical Status of Multi-Peptide Formulation Effects

Evidence Gaps and the Preclinical Status of Multi-Peptide Formulation Effects

The most important point in any discussion of GHK-Cu and Glow Blend in keratinocyte models: separating copper signaling from multi-peptide formulation effects is this, the blend has never been tested as a unit in a published keratinocyte study. Every claim about how the three peptides work together in epidermal tissue is an extrapolation from single-peptide preclinical data.

GHK-Cu alone does have the highest evidence tier among the three components in skin contexts. There is at least one small randomized controlled trial (CO2-laser-resurfaced skin, n=13) showing improved patient-rated skin quality (P=0.04), though blinded assessor ratings showed no significant difference in redness or wrinkles versus control. This makes GHK-Cu's topical human evidence notable compared to the purely preclinical status of BPC-157 and TB-500 in skin applications.

The Glow Blend and related formulations such as KLOW (combining GHK-Cu with KPV) are currently supplied as research-grade materials. Published safety data for all three Glow components come from animal models, in vitro studies, or topical human applications of GHK-Cu alone. Long-term systemic safety of injected multi-peptide combinations is essentially uncharacterized. Research suppliers consistently emphasize that the blend is intended for in vitro or animal use and is not approved for human injection. For researchers comparing suppliers before sourcing blend components, the peptide supplier comparisons guide interpreting PeptideTech and PeptideSC is a practical reference. Broader guidance on sourcing is also available at where to buy peptides.

Critical gaps that future keratinocyte studies should address:

  1. Does TB-500 enhance GHK-Cu-driven scratch-assay closure, or does it operate redundantly?
  2. Does BPC-157 contribute measurable readouts in avascular epidermal monolayers?
  3. Are copper availability and ARE activation affected by the presence of BPC-157 or TB-500 at physiological concentrations?
  4. Do any of the three peptides interfere with each other's receptor binding or intracellular signaling at the concentrations used in blend formulations?

Until these questions are answered with controlled keratinocyte data, the Glow Blend should be treated as a hypothesis-generating platform rather than a validated synergistic protocol.


Conclusion

Keratinocyte models give researchers a more direct window into epidermal biology than fibroblast systems, and GHK-Cu's copper signaling record in those models is the strongest element of the Glow Blend's evidence base. Nrf2 activation, barrier protein expression, proliferation indices, and scratch-assay migration rates all offer concrete, measurable readouts that can isolate copper-dependent effects from the noise of a multi-peptide formulation.

Actionable next steps for researchers:

  • Design single-peptide keratinocyte controls before introducing the full Glow Blend to any assay.
  • Select readouts specific to the epidermis: barrier protein expression, oxidative stress markers, proliferation, and scratch-closure rate rather than collagen deposition alone.
  • Apply the tendon-model lesson, combination did not outperform single agents, and treat synergy as a hypothesis requiring proof, not a default assumption.
  • Source research-grade materials from documented, third-party-tested suppliers and maintain strict QC records throughout experimental design.
  • Avoid extrapolating preclinical keratinocyte findings to clinical or injectable contexts without formal pharmacokinetic, toxicity, and interaction data.

The science of copper signaling in skin is well-grounded. The science of multi-peptide formulation effects in keratinocyte-specific models is, as of 2026, still an open question worth answering rigorously.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/ghk-cu-and-glow-blend-in-keratinocyte-models-separating-copper-signaling-from-mu.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-23 13:05:022026-10-23 13:05:02GHK-Cu and Glow Blend in Keratinocyte Models: Separating Copper Signaling From Multi-Peptide Formulation Effects
Advanced Glycation End-Products in Peptide Research: Measuring Glycemic Memory, Collagen Crosslinking, and Tissue Repair

Advanced Glycation End-Products in Peptide Research: Measuring Glycemic Memory, Collagen Crosslinking, and Tissue Repair

October 22, 2026/0 Comments/in Uncategorized/by

Collagen laid down decades ago still carries the chemical signature of every glucose spike it ever witnessed. That silent biochemical record, preserved in the very scaffolding of skin, tendons, discs, and blood vessels, is what researchers now call glycemic memory, and it explains why vascular complications persist even after blood sugar is brought under control. Understanding advanced glycation end-products in peptide research: measuring glycemic memory, collagen crosslinking, and tissue repair has therefore become one of the most consequential frontiers in translational biology, sitting at the intersection of metabolic disease, structural biology, and next-generation peptide science.

Key Takeaways

  • AGEs accumulate irreversibly in long-lived matrix proteins, encoding years of metabolic history independently of current blood glucose.
  • Skin autofluorescence (SAF) provides a non-invasive window into cumulative AGE burden and predicts micro- and macrovascular risk.
  • AGE-driven collagen crosslinking stiffens tissues, impairs macrophage-mediated remodeling, and delays wound healing.
  • Peptides such as BPC-157, GHK-Cu, and retatrutide-adjacent GLP-class compounds occupy distinct but complementary roles in AGE-associated tissue repair models.
  • Three therapeutic directions dominate current research: limiting new AGE formation, breaking established crosslinks, and restoring matrix turnover.

What Are AGEs and Why Do They Encode Glycemic Memory

Advanced glycation end-products form when reducing sugars react non-enzymatically with free amino groups on proteins, lipids, and nucleic acids, a cascade known as the Maillard reaction. In short-lived proteins this chemistry is a nuisance. In long-lived extracellular matrix proteins such as collagen type I, elastin, and basement membrane laminins, it is a permanent structural edit.

What Are AGEs and Why Do They Encode Glycemic Memory

Because collagen in tendons, skin, and arterial walls turns over on timescales of years to decades, AGE modifications accumulate progressively. Lysine and arginine residues are the primary targets, and the resulting crosslinks, including pentosidine and carboxymethyl-lysine, alter fiber geometry, reduce compliance, and resist proteolytic clearance. The tissue therefore retains a biochemical record of prior hyperglycemia long after HbA1c normalizes. This is the mechanistic core of glycemic memory: past glucose exposure continues to drive complication risk through matrix chemistry rather than circulating glucose.

Skin autofluorescence (SAF) has emerged as the most practical non-invasive readout of this burden. SAF correlates with HbA1c measured over the preceding three to ten years across type 1, type 2, and gestational diabetes populations, and it predicts both current and future micro- and macrovascular complications. Crucially, SAF provides information about cumulative metabolic injury that a single-time-point HbA1c measurement cannot capture, making it a genuine "memory" biomarker rather than a snapshot.

"AGEs encode lasting tissue damage despite later normoglycemia, measuring them changes what clinicians and researchers know about a patient's risk."


Collagen Crosslinking, RAGE Signaling, and Impaired Tissue Repair

The structural consequences of AGE-mediated crosslinking extend far beyond stiffness. In tendon tissue, non-enzymatic crosslinks accumulate at lysine and arginine residues in telopeptide regions, degrading biomechanical properties and activating the receptor for AGEs (RAGE). RAGE-dependent signaling disrupts extracellular matrix integrity and impairs wound healing, positioning AGE load as a modifiable variable in connective tissue repair quality.

Collagen Crosslinking, RAGE Signaling, and Impaired Tissue Repair

In the intervertebral disc, AGEs covalently modify collagen and elastin, promoting abnormal crosslinking and tissue stiffening. Animal model studies with AGE crosslink breakers, including N-phenacylthiazolium bromide (PTB) and ALT-711, partially reverse AGE-induced stiffness, offering proof of concept for structurally targeted therapy.

Fibrotic liver tissue illustrates the repair-blocking dimension most starkly. AGE-driven crosslinking alters collagen architecture and impairs macrophage-mediated matrix remodeling, effectively locking tissues in a state of defective repair. The same principle applies to skin, where AGE crosslinks with structural proteins including collagen, elastin, fibronectin, and laminin contribute to stiffening, reduced elasticity, and delayed wound healing.

Epigenetic mechanisms add another layer. Chronic AGE stimulation, for example, via AGE-albumin exposure in renal tubular cells, reduces EZH2 and H3K27me3 levels, upregulating injury-related genes at the chromatin level. This histone modification persists after glucose normalization, linking AGE biology directly to the epigenetic machinery of metabolic memory. A 2026 synthesis of trained immunity research further proposes that AGEs interact with innate immune reprogramming to sustain inflammatory tone and impair repair responses, explaining interindividual variability that AGE accumulation alone cannot account for.


Advanced Glycation End-Products in Peptide Research: Measuring Glycemic Memory, Collagen Crosslinking, and Tissue Repair Through Targeted Interventions

Three therapeutic directions now define how advanced glycation end-products in peptide research frame targeting strategies: limiting new AGE formation, breaking established crosslinks, and restoring matrix turnover.

Advanced Glycation End-Products in Peptide Research: Measuring Glycemic Memory, Collagen Crosslinking, and Tissue Repair Thro

1. Limiting new AGE formation
Carbonyl scavengers and RAGE antagonists reduce the substrate available for further glycation. In metabolic research contexts, GLP-1 receptor agonists, including compounds related to retatrutide (a GLP-1/GIP/glucagon triple agonist), reduce chronic hyperglycemia and thereby slow the rate of new AGE deposition. Researchers sourcing retatrutide for sale in preclinical contexts often frame glycemic control as the upstream lever for AGE management.

2. Breaking established crosslinks
Small-molecule breakers (PTB, ALT-711) represent the classical approach. Peptide-based crosslink breakers and peptide mimetics are now catalogued as emerging candidates alongside established carbonyl scavengers, particularly for collagen-rich tissues with clear structural endpoints.

3. Restoring matrix turnover and tissue compliance
This is where peptides such as BPC-157 and GHK-Cu become directly relevant. The BPC-157 core peptides documentation describes a body pentadecapeptide with well-characterized effects on angiogenesis, tendon-to-bone healing, and extracellular matrix remodeling, precisely the endpoints most impaired by AGE-driven crosslinking. GHK-Cu (glycine-histidine-lysine copper complex) upregulates matrix metalloproteinases and promotes collagen synthesis, offering a complementary matrix-renewal mechanism.

SS-31, a mitochondria-targeted peptide, addresses the oxidative stress dimension that AGEs amplify. Studies on SS-31 peptide benefits suggest it reduces reactive oxygen species generated downstream of RAGE activation, potentially interrupting the epigenetic reinforcement loop that sustains glycemic memory. Researchers have also examined SS-31 and MOTS-c combinations for metabolic and mitochondrial synergy.

GLP-2-related compounds are relevant to intestinal matrix repair, where AGE-modified basement membrane components impair epithelial turnover. The GLP-3 peptide signaling pathway article outlines receptor-level mechanisms applicable to gut mucosal repair models.

Research framing note: Distinguishing acute glucose changes from long-lived matrix effects is critical when designing AGE studies. HbA1c reflects the prior 8-12 weeks; SAF and tissue AGE biomarkers reflect years. Peptide interventions targeting matrix turnover operate on the structural timescale, not the glycemic one.
Biomarker Timescale Reflected Practical Use
Fasting glucose Hours Acute glycemic state
HbA1c 8-12 weeks Short-term control
Skin autofluorescence 3-10 years Cumulative AGE burden
Tissue collagen AGEs Decades Structural glycemic memory

For researchers evaluating supplier quality before initiating AGE-related studies, peptide supplier comparisons offer a useful framework for interpreting purity documentation.


Conclusion

Advanced glycation end-products in peptide research represent more than a niche biochemistry topic, they are the molecular link between metabolic history and structural tissue fate. The key actions for researchers in 2026 are clear:

  • Measure AGE burden correctly. Use SAF or tissue-specific AGE assays rather than relying solely on HbA1c when studying chronic complications or long-term tissue remodeling.
  • Match the peptide to the mechanism. BPC-157 and GHK-Cu target matrix turnover; SS-31 targets oxidative RAGE signaling; GLP-class peptides address upstream hyperglycemia. These are complementary, not interchangeable.
  • Choose structural endpoints. Collagen crosslink density, tissue stiffness, and biomechanical properties are the most informative surrogates for reversing glycemic memory in preclinical models.
  • Prioritize source quality. AGE research depends on reproducible peptide preparations; verify purity data before drawing mechanistic conclusions.

The intersection of AGE biology and targeted peptide science is where some of the most actionable translational discoveries are likely to emerge over the next few years. The structural record written by decades of glycation can, incrementally, be revised.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/advanced-glycation-end-products-in-peptide-research-measuring-glycemic-memory-co-1.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-22 13:04:182026-10-22 13:04:18Advanced Glycation End-Products in Peptide Research: Measuring Glycemic Memory, Collagen Crosslinking, and Tissue Repair
BPC-157 and TB-500 Combination Research: How to Test Additivity Without Assuming Synergy

BPC-157 and TB-500 Combination Research: How to Test Additivity Without Assuming Synergy

October 18, 2026/0 Comments/in Uncategorized/by

Only three small pilot human studies of BPC-157 exist in the published literature, with a combined enrollment of roughly 30 participants, and not a single controlled trial has tested BPC-157 alongside TB-500 in people. Yet use of the so-called "Wolverine stack", combining these two peptides, has surged 33-fold between 2020 and 2026 in one observational dataset, driven largely by preclinical rodent data and influencer-led extrapolation. The gap between that popularity and the actual evidence base makes rigorous BPC-157 and TB-500 combination research not just useful, but necessary.

Key Takeaways

  • No human clinical trial has ever tested BPC-157 and TB-500 together; all combination claims are extrapolated from animal or cell data.
  • Synergy is a specific, measurable pharmacological claim, it must be distinguished from simple additivity using factorial designs and isobolograms.
  • The correct experimental framework uses four groups: vehicle control, BPC-157 alone, TB-500 alone, and the combination.
  • Relevant outcome measures include matrix remodeling markers, angiogenesis indices, barrier recovery scores, inflammation panels, and cell viability assays.
  • Researchers should apply formal interaction statistics before reporting any combined effect as synergistic rather than merely additive or even antagonistic.

Why the Synergy Assumption Is a Research Problem

The phrase "synergy" is used loosely in peptide communities, but in pharmacology it carries a precise meaning: two agents together produce an effect greater than the sum of their individual effects at equivalent doses. Calling the BPC-157 and TB-500 combination synergistic without testing that claim is not a minor semantic issue, it shapes dosing rationale, safety expectations, and downstream regulatory arguments.

Why the Synergy Assumption Is a Research Problem

BPC-157 is a synthetic pentadecapeptide derived from a gastric protein. Its primary research interests include barrier recovery in gastrointestinal epithelium, modulation of nitric oxide signaling, and tendon-to-bone interface healing. TB-500 is a synthetic fragment of thymosin-beta-4, a protein involved in actin sequestration and cell migration. Its preclinical research focus centers on angiogenesis, satellite cell activation, and extracellular matrix remodeling. These two peptides act through partially overlapping but mechanistically distinct pathways.

That partial overlap is exactly why assuming synergy is problematic. When two agents share downstream targets, such as VEGF-driven angiogenesis or TGF-beta-mediated collagen synthesis, their combined effect may be purely additive, meaning each contributes its portion without amplifying the other. Some preclinical rodent models of tendon and muscle injury have shown that concurrent BPC-157 and TB-500 administration accelerated healing timelines compared with either peptide alone, with histological evidence of more organized collagen fiber deposition and earlier vascular network formation. However, none of those studies presented isobolograms, dose-response surfaces, or formal interaction statistics. Descriptive observations of faster healing cannot distinguish true synergy from additivity, and at least one preclinical summary noted that combined treatment did not provide additional benefit over individual peptides in certain models, directly undermining the universal synergy assumption.

"Descriptive observations of faster healing cannot distinguish true synergy from additivity without a formal interaction test."


The Factorial Design Framework for BPC-157 and TB-500 Combination Research

The gold standard for testing whether two agents interact, rather than simply add, is the factorial experiment. Applied to BPC-157 and TB-500 combination research, this means assigning subjects or cell preparations to four groups in a 2×2 matrix.

The Factorial Design Framework for BPC-157 and TB-500 Combination Research

The four required groups:

Group BPC-157 TB-500
Vehicle control No No
BPC-157 alone Yes No
TB-500 alone No Yes
Combination Yes Yes

Without all four groups, no interaction can be calculated. Many published preclinical studies compare only the combination group against a vehicle control, which conflates the individual contributions and makes it impossible to isolate any interaction term.

Selecting the right outcome measures matters equally. For BPC-157 and TB-500 combination research to generate interpretable data, endpoints should map to each peptide's known mechanism:

  • Matrix remodeling: collagen type I/III ratio, MMP-2 and MMP-9 activity, hydroxyproline content
  • Angiogenesis: CD31 staining density, VEGF expression, tube-formation assays in endothelial cells
  • Barrier recovery: transepithelial electrical resistance, tight-junction protein expression (ZO-1, occludin)
  • Inflammation: IL-6, TNF-alpha, IL-10 cytokine panels at defined time points
  • Cell viability: MTT or ATP-based assays to confirm non-toxicity at tested concentrations

Once dose-response curves are established for each agent individually, the isobologram method plots equieffective dose combinations. Points falling on the line of additivity confirm simple additivity; points below it indicate synergy; points above indicate antagonism. The combination index (CI) derived from the Chou-Talalay method provides a quantitative summary statistic that is reportable and reproducible.


Applying the Framework: Practical Steps for Researchers

Translating the factorial framework into a workable protocol requires sequencing experiments carefully to avoid wasting resources on combination doses that fall outside the informative range.

Applying the Framework: Practical Steps for Researchers

Step 1, Establish single-agent dose-response curves. Run BPC-157 and TB-500 individually across at least five concentrations bracketing the expected EC50. Use the outcome measures listed above, not just a single readout. This step is non-negotiable; without it, combination doses are chosen arbitrarily.

Step 2, Select fixed-ratio combination doses. Choose doses that correspond to fractions of each agent's EC50 (for example, 1:1, 2:1, 1:2 ratios). This preserves the ability to construct a meaningful isobologram.

Step 3, Run the full factorial experiment. Include vehicle, each single agent at each selected dose, and the combination at matched ratios. Blind outcome assessors to group assignment.

Step 4, Calculate the interaction index. Apply the CI method or a two-way ANOVA interaction term. Report the confidence interval around the interaction estimate, not just the point estimate.

Step 5, Replicate before concluding. A single experiment showing a sub-additive or supra-additive result is not sufficient. Biological replicates across at least two independent cell passages or animal cohorts are required before any interaction claim is published.

Researchers sourcing peptides for in vitro or preclinical work should consult a peptide supplier comparisons guide to evaluate purity documentation, as impure preparations introduce confounders that invalidate interaction analyses. Purity certificates and mass spectrometry data should accompany any research-grade material. For those exploring related dual-peptide interaction designs, the synergy of LL-37 and SS-31 framework offers a parallel methodological reference. Broader sourcing considerations are covered in the where to buy peptides resource. Researchers interested in other peptides with overlapping angiogenic or tissue-repair mechanisms may also find the GHK-Cu peptide sourcing guide and the SS-31 mitochondrial research themes overview useful for contextualizing multi-peptide experimental designs. For those examining growth-factor-adjacent peptides in musculoskeletal models, IGF-1 LR3 research products represent another mechanistically relevant comparison arm.


Conclusion

BPC-157 and TB-500 combination research sits at a critical juncture in 2026. Preclinical observations are intriguing, but they have been systematically over-interpreted as proof of synergy when the data support, at best, a hypothesis worth testing. The human evidence base, three small pilot BPC-157 studies, no TB-500 human trials, and no combination data whatsoever, cannot support clinical claims of any kind, let alone synergistic ones.

Actionable next steps for researchers:

  1. Design every combination experiment with all four factorial groups before collecting a single data point.
  2. Establish individual dose-response curves first; do not skip to combination testing.
  3. Choose outcome measures that map to the specific mechanisms of each peptide: matrix remodeling, angiogenesis, barrier recovery, inflammation, and cell viability.
  4. Apply the isobologram or CI method and report interaction confidence intervals.
  5. Replicate findings across independent biological systems before drawing conclusions about interaction type.
  6. Clearly label any findings as preclinical and resist extrapolating to human dosing or clinical benefit.

The scientific value of BPC-157 and TB-500 combination research will only be realized when the field replaces assumption-driven stacking narratives with interaction-design frameworks built on measurable, reproducible pharmacological evidence.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/bpc-157-and-tb-500-combination-research-how-to-test-additivity-without-assuming.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-18 13:03:432026-10-18 13:03:43BPC-157 and TB-500 Combination Research: How to Test Additivity Without Assuming Synergy
Page 1 of 41234
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top