Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: glp-1 receptor agonist

Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design

Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design

October 31, 2026/0 Comments/in Uncategorized/by

Nearly 24 percent of adults worldwide now meet criteria for obesity-related metabolic disease, yet two compounds under research scrutiny, retatrutide and tesofensine, attempt to address that burden through fundamentally different biological mechanisms. Understanding Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design is not simply an academic exercise. The receptor class each compound targets determines the endpoints researchers can reasonably measure, the safety signals they must monitor, and the patient populations they can safely study.

Key Takeaways

  • Retatrutide is a triple hormone receptor agonist (GLP-1R, GIPR, GcgR); tesofensine is a small-molecule triple monoamine reuptake inhibitor, these are fundamentally different pharmacological classes.
  • Receptor biology drives endpoint selection: hormone agonism supports glycemic, hepatic, renal, and cardiovascular endpoints, while monoamine blockade demands central nervous system and cardiovascular safety monitoring.
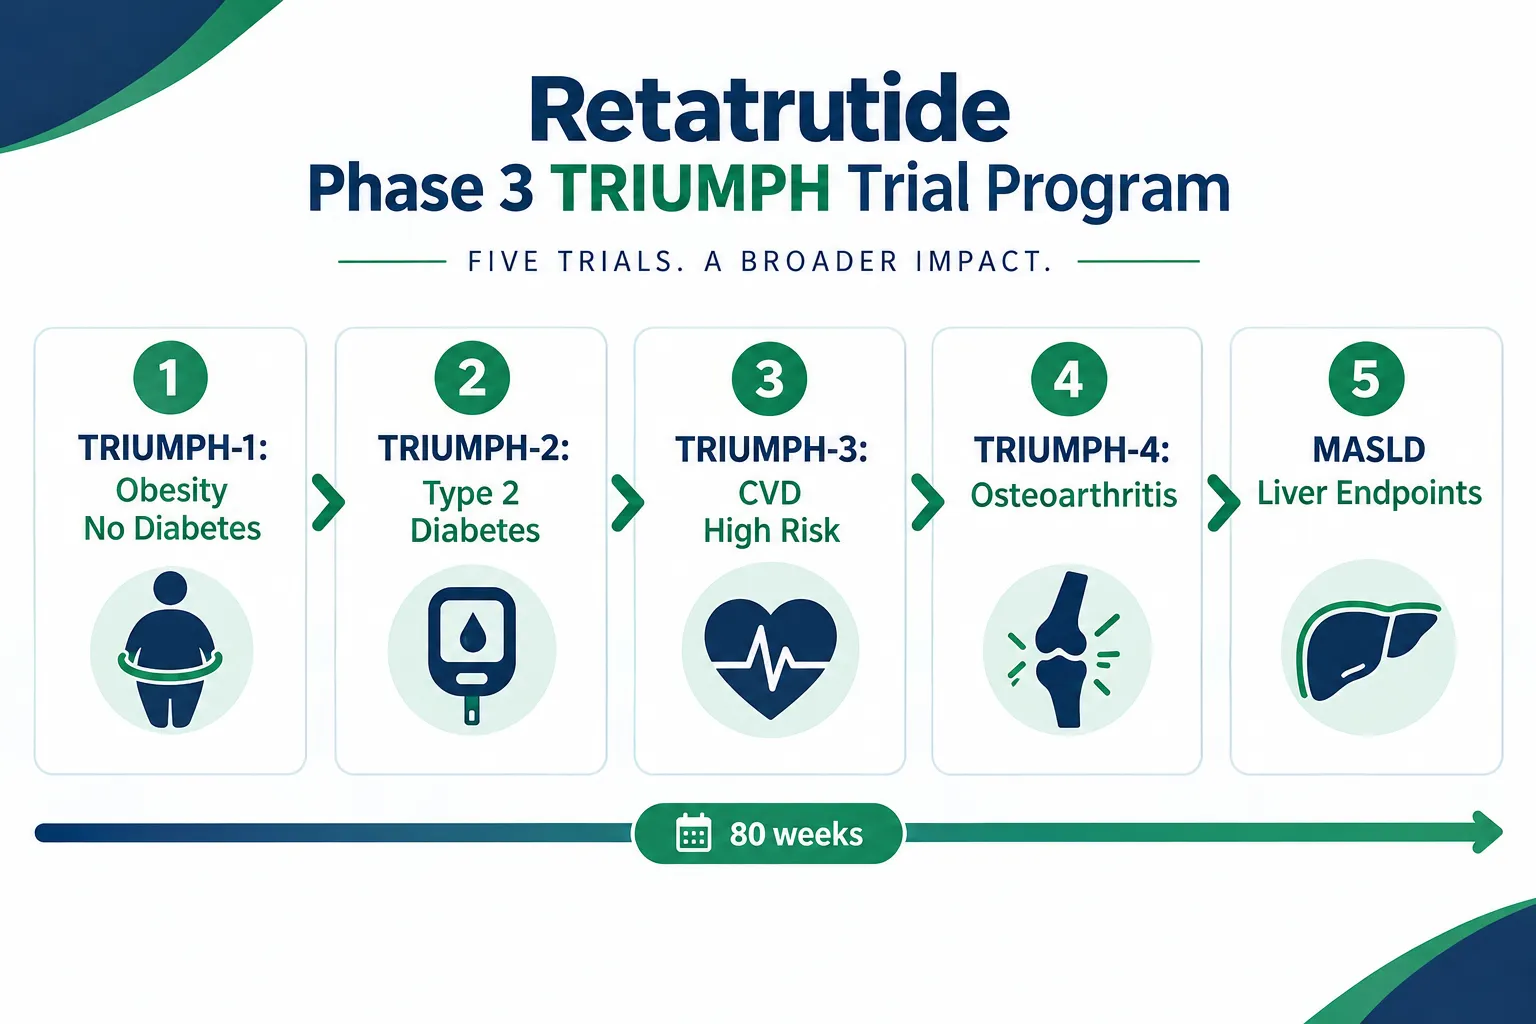
  • Retatrutide's TRIUMPH-1 phase 3 data set a new efficacy benchmark for obesity pharmacotherapy.
  • Tesofensine remains a niche research compound with a narrower endpoint profile and a more cautious regulatory trajectory.
  • Choosing between these mechanisms as a research scaffold determines which patient populations can ethically be included in a trial.

Distinct Mechanisms: Triple Hormone Agonism vs Monoamine Reuptake Inhibition
Distinct Mechanisms: Triple Hormone Agonism vs Monoamine Reuptake Inhibition

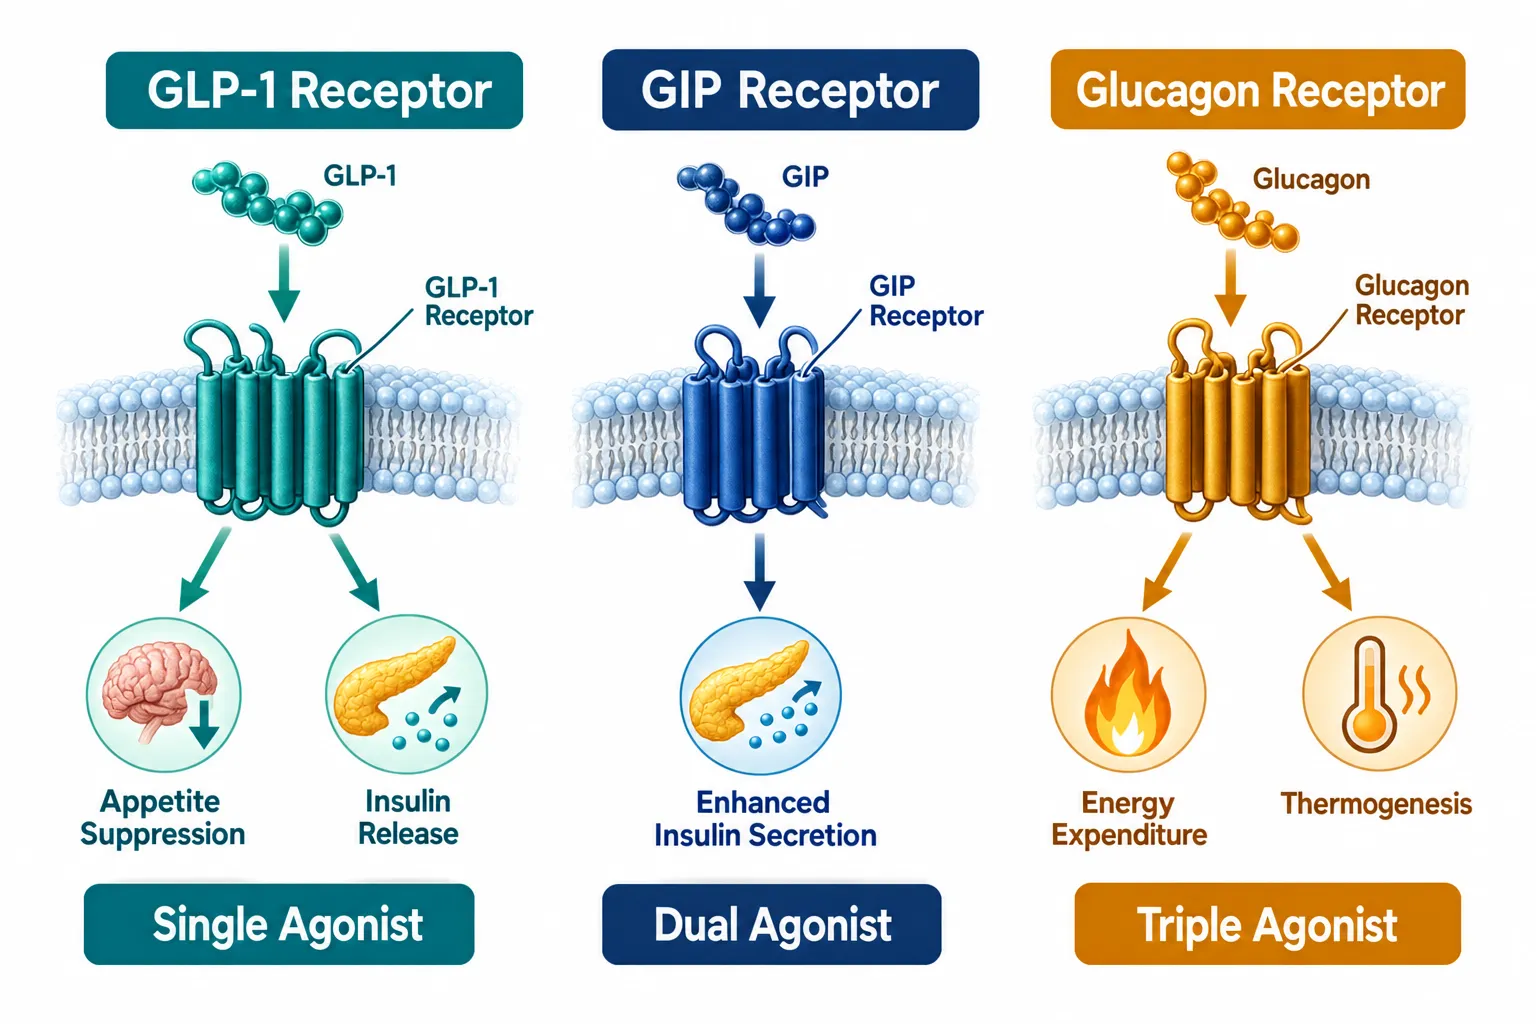
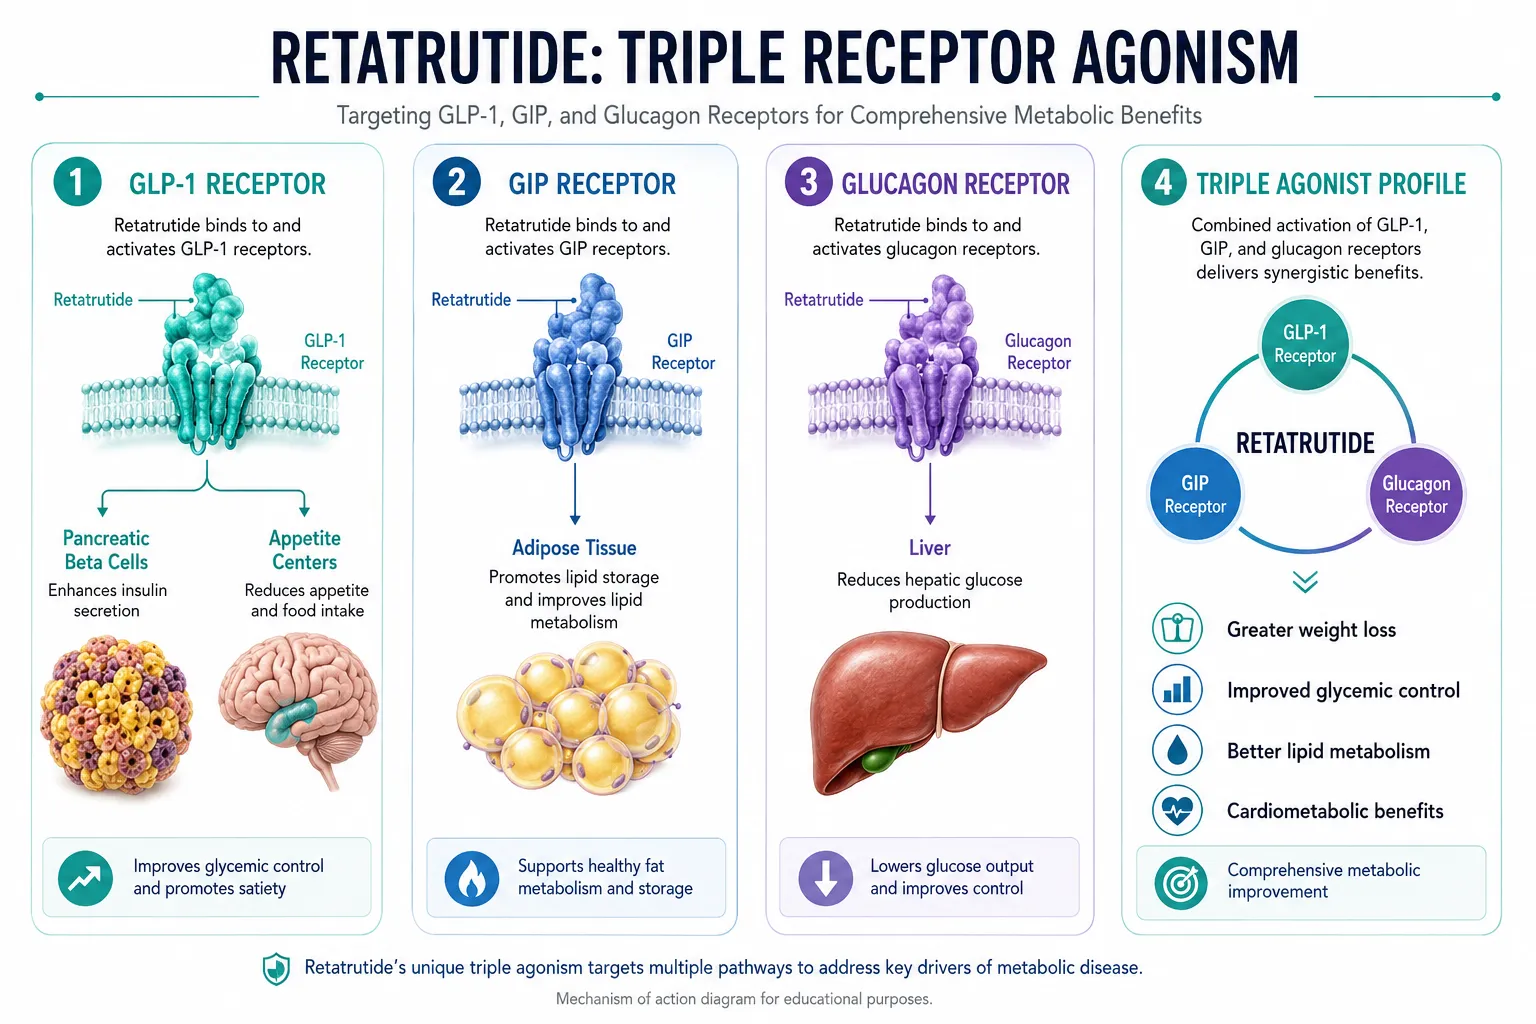
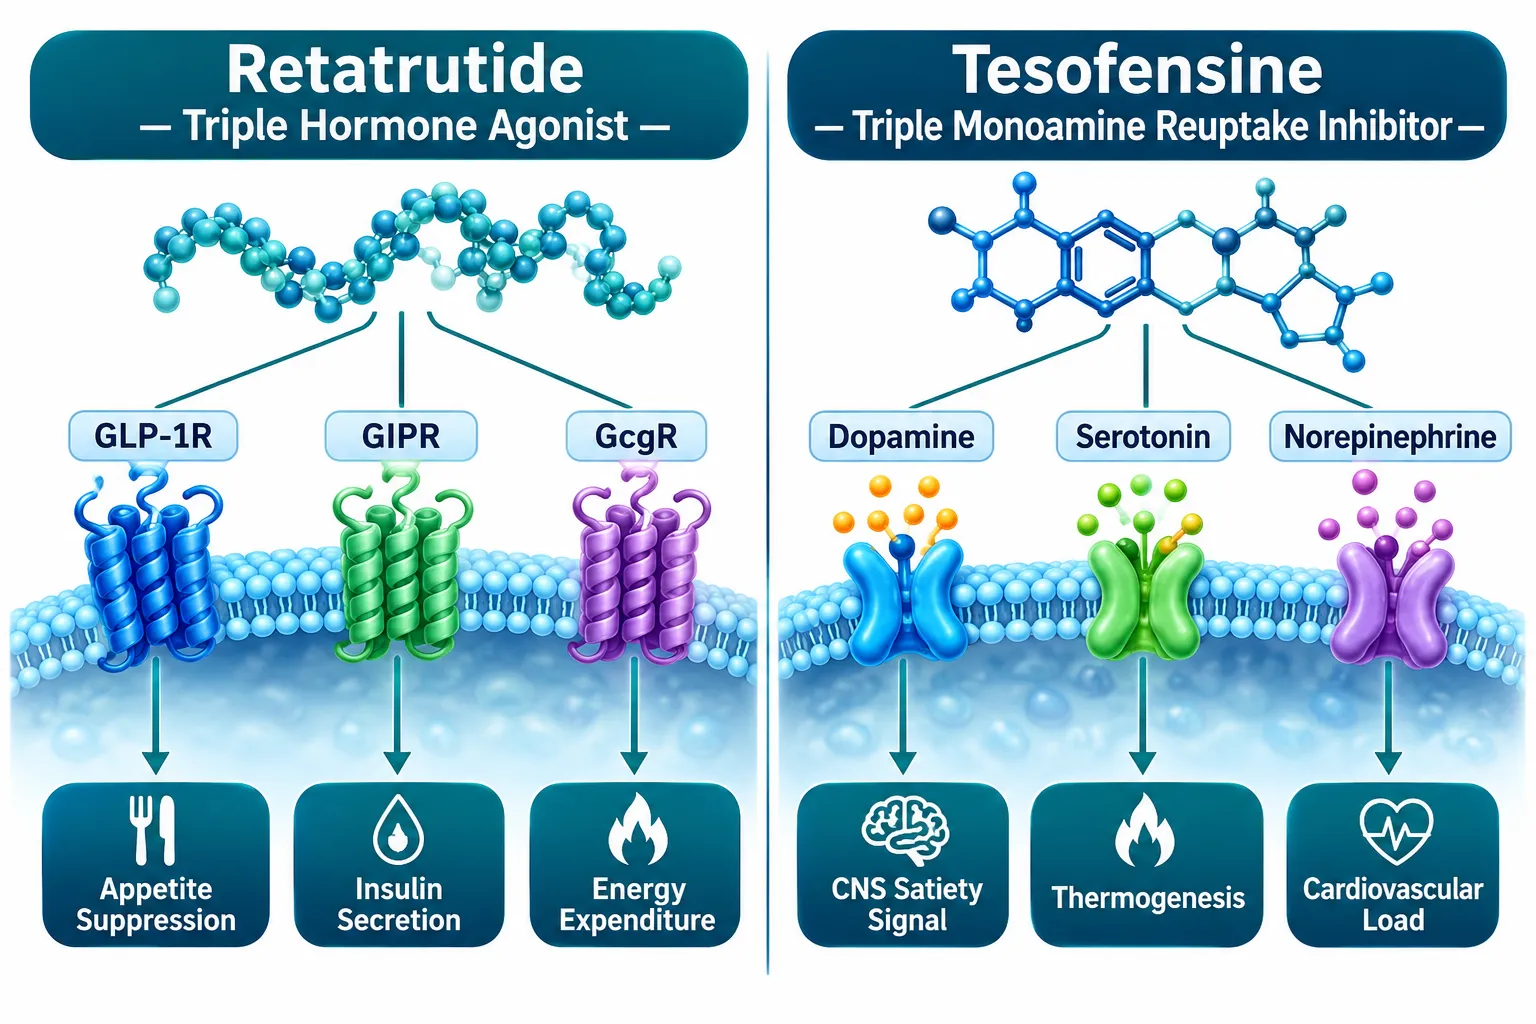
Retatrutide is a peptide-based triple agonist that activates three G-protein-coupled receptors (GPCRs): the glucagon-like peptide-1 receptor (GLP-1R), the glucose-dependent insulinotropic polypeptide receptor (GIPR), and the glucagon receptor (GcgR). Each receptor axis contributes a distinct metabolic function. GLP-1R activation reduces appetite and slows gastric emptying. GIPR activation enhances insulin release and may augment the satiety signal from GLP-1R. GcgR activation increases hepatic glucose output at low doses but, more importantly at therapeutic doses, raises energy expenditure through brown adipose tissue activation.

Tesofensine is a small molecule, not a peptide, that blocks the reuptake of dopamine, serotonin, and norepinephrine in the central nervous system. This monoamine reuptake inhibition reduces food intake primarily through central appetite suppression and may modestly increase thermogenesis via sympathomimetic activity. Because it does not engage endocrine GPCRs, it produces no direct incretin effect and no glucagon-mediated boost to energy expenditure.

"The receptor class a compound targets is the single most important variable a metabolic research team will confront when designing a trial from the ground up."

This mechanistic divide explains why researchers exploring visceral fat research increasingly orient their protocols around GPCR-based compounds rather than monoamine modulators: the hormone agonist axis provides multiple measurable tissue-level endpoints that monoamine signaling simply cannot reach.


Cardiometabolic Endpoints: Where Receptor Biology Shapes Research Design
Cardiometabolic Endpoints: Where Receptor Biology Shapes Research Design

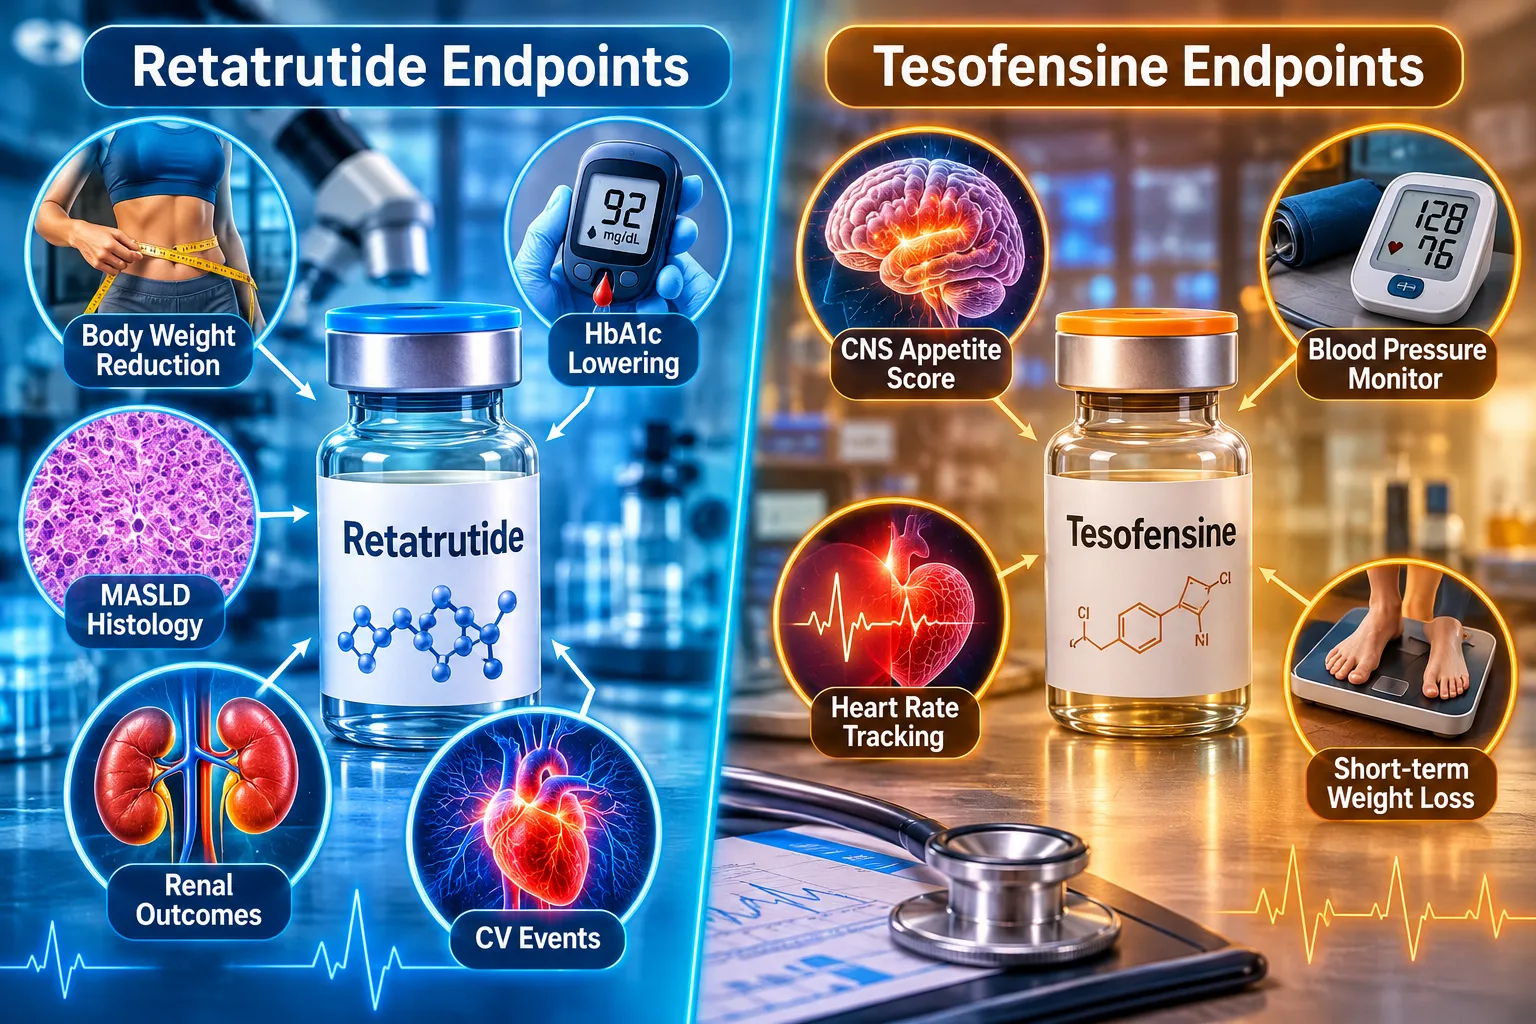
The depth of measurable outcomes differs sharply between these two pharmacological classes. Retatrutide's TRIUMPH-1 phase 3 trial data, the most rigorous dataset available for the compound, demonstrated average body weight reductions that surpassed any previously approved pharmacotherapy in comparable populations. Beyond weight, the hormone receptor axes produce quantifiable effects across a broad endpoint portfolio.

Retatrutide endpoint categories in active investigation:

  • Glycemia: HbA1c reduction and fasting glucose in type 2 diabetes
  • Hepatic histology: Liver fat fraction and inflammation scores relevant to metabolic dysfunction-associated steatotic liver disease (MASLD)
  • Cardiovascular: Blood pressure, lipid panels, and emerging cardiovascular outcome trials
  • Renal: Albuminuria and estimated glomerular filtration rate (eGFR)
  • Musculoskeletal: Osteoarthritis pain and functional scores
  • Sleep: Apnea severity indices

Researchers sourcing retatrutide for clinical trial work can therefore design basket-style protocols that capture multi-system effects within a single compound arm.

Tesofensine's endpoint landscape is narrower. The monoamine mechanism does produce meaningful short-term weight reduction, but the primary safety concern, elevated heart rate and blood pressure from norepinephrine signaling, constrains the populations eligible for inclusion. Patients with pre-existing cardiovascular disease, which represents a large share of the high-BMI population, require careful screening and more intensive monitoring when tesofensine is the study compound.

Key monitoring differences by mechanism class:

Monitoring Domain Retatrutide (GPCR Agonist) Tesofensine (Monoamine Inhibitor)
Gastrointestinal tolerability Titration-managed nausea Minimal
Cardiovascular Blood pressure, lipid trending Heart rate, blood pressure, primary concern
CNS effects Minimal Mood, insomnia, anxiety screening
Glycemic safety Hypoglycemia in T2D combos Not applicable

Trial Population Design and Regulatory Trajectory
Trial Population Design and Regulatory Trajectory

Understanding Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design at the population level reveals another critical divergence. Because retatrutide's titration profile manages gastrointestinal side effects gradually and does not carry significant sympathomimetic cardiovascular load, trial teams can include patients with severe obesity (BMI above 40) and those with established cardiovascular disease. This broadens the generalizability of findings and aligns with regulatory expectations for a broad obesity pharmacotherapy label.

Tesofensine's sympathomimetic activity demands that researchers apply stricter cardiovascular exclusion criteria. This effectively limits the study population to lower-risk participants, which may inflate observed efficacy relative to the general target population, a recognized limitation in earlier phase 2 work.

From a regulatory standpoint, retatrutide is advancing toward new drug application filings following strong phase 3 readouts. Expert and association commentary in 2026 has described it as the first "triple hormone therapy" for obesity, a framing that reflects genuine novelty in the GPCR agonist space. Tesofensine remains a niche investigational compound without a clear path to broad regulatory approval in major markets, making it more relevant as a mechanistic research tool than a clinical development candidate.

Researchers working with related peptide scaffolds can explore resources on GLP-3 triple agonist research planning to understand how multi-receptor designs are being structured across the broader incretin space. Those sourcing materials for cardiometabolic studies should also review AOD 9604 research method notes on storage and traceability for best practices applicable across metabolic peptide protocols.

For researchers looking at specific retatrutide material formats, catalog options such as RETA 20mg for sale and GLP-3 RETA 30mg reflect the range of dosing configurations available for pre-clinical and translational work. Mitochondrial energy expenditure pathways relevant to GcgR activation are explored further in SS-31 mitochondrial research themes.


Conclusion

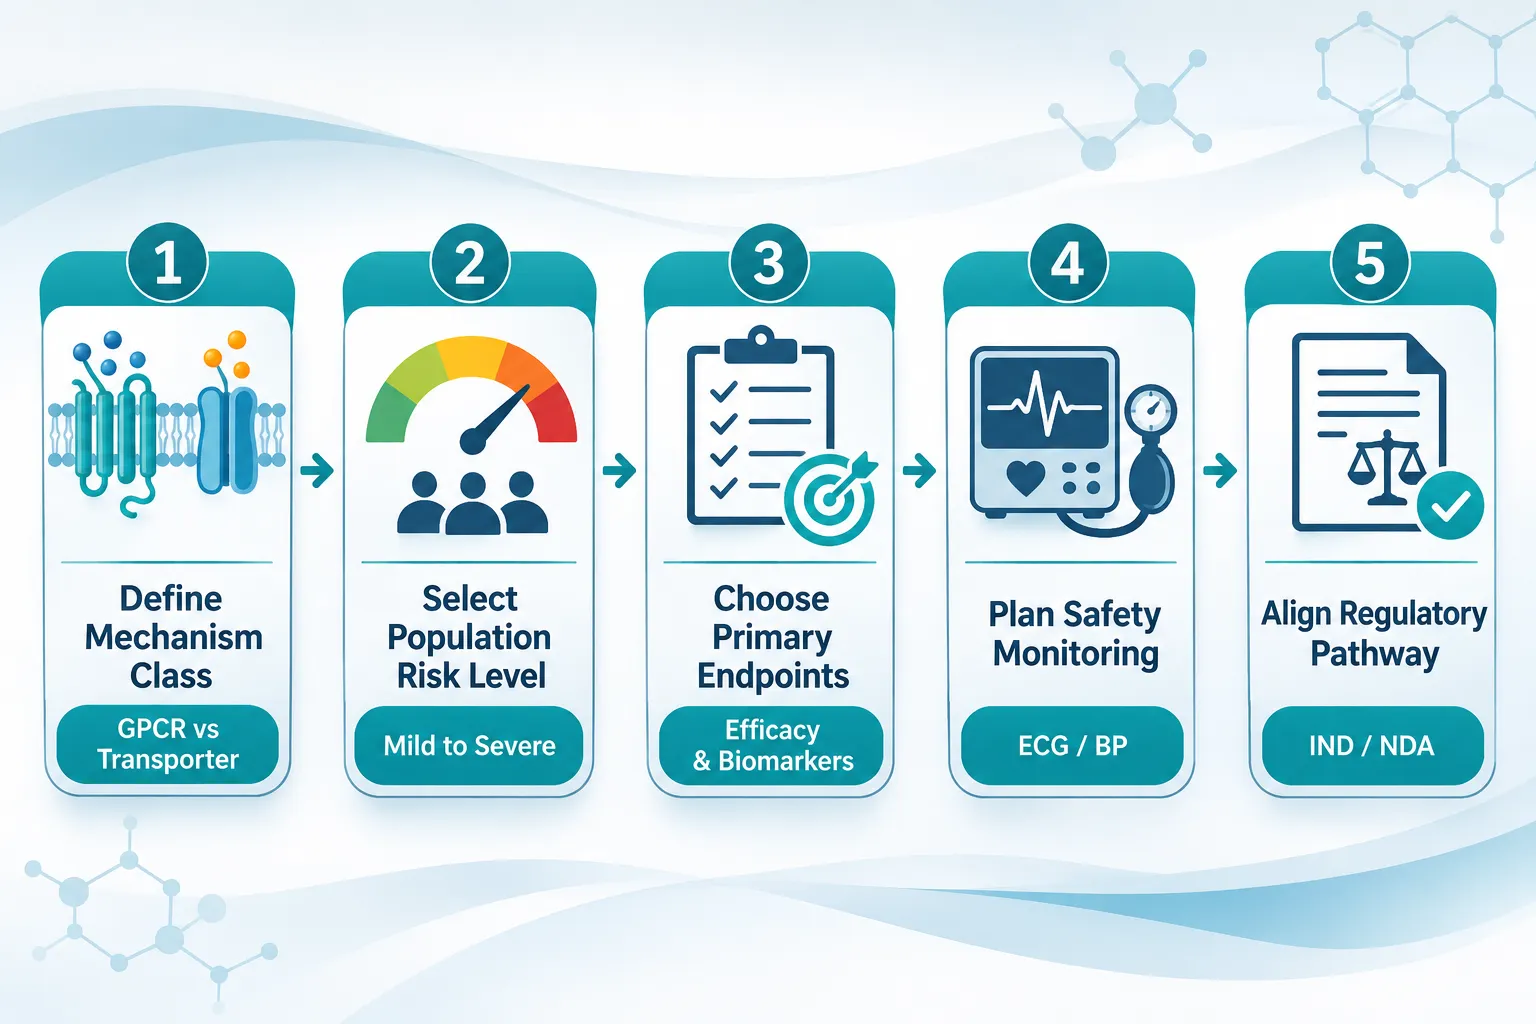
The comparison of Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design ultimately reduces to one foundational question: which receptor class aligns with the metabolic questions a research team wants to answer?

Retatrutide's triple GPCR agonism enables broad, multi-system endpoint selection, inclusive trial populations, and a regulatory trajectory consistent with eventual clinical adoption. Tesofensine's monoamine reuptake inhibition is a useful mechanistic tool for studying central appetite circuitry, but its cardiovascular monitoring demands and narrow endpoint scope limit its utility in high-risk populations.

Actionable steps for research teams in 2026:

  1. Map receptor targets to endpoints first, confirm that the compound's mechanism can actually produce measurable change at your chosen endpoint before committing to a protocol.
  2. Assess population risk tolerance, monoamine reuptake inhibition requires tighter cardiovascular exclusion criteria; plan for this during power calculations.
  3. Align safety monitoring to mechanism class, GPCR agonists demand GI tolerability tracking and titration schedules; monoamine inhibitors demand heart rate and blood pressure surveillance.
  4. Consider multi-system designs for GPCR agonists, the breadth of retatrutide's receptor engagement supports basket-style trial architectures that would be impractical with monoamine-based compounds.
  5. Track regulatory signals closely, retatrutide's development timeline is accelerating; research programs designed around its mechanism are more likely to translate into clinical practice.

Choosing the right mechanistic scaffold is not merely a pharmacology decision, it is a research design decision that shapes every downstream element of a study.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-vs-tesofensine-how-receptor-biology-and-monoamine-signaling-shape-me.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-31 13:05:202026-10-31 13:05:20Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design
GLP-1 Pills and Research-Use Peptides: How to Compare Oral Delivery, Gastric Stability, and Exposure Without Making Clinical Claims

GLP-1 Pills and Research-Use Peptides: How to Compare Oral Delivery, Gastric Stability, and Exposure Without Making Clinical Claims

October 23, 2026/0 Comments/in Uncategorized/by

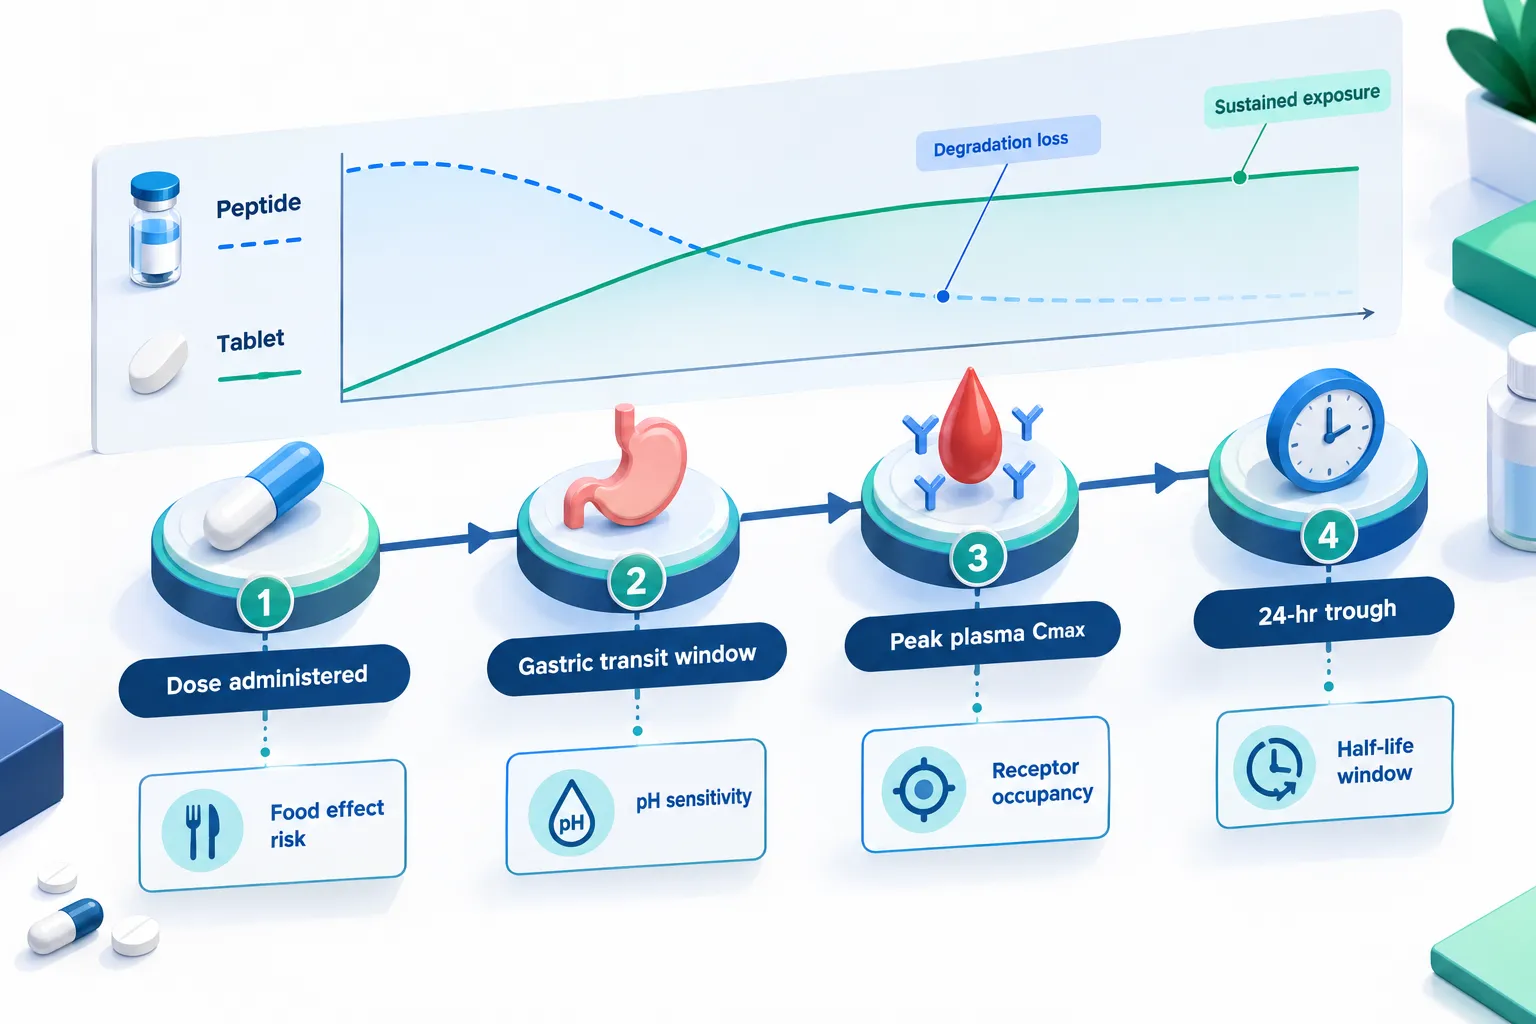
Oral bioavailability of approximately 79% for a GLP-1 receptor agonist was considered nearly impossible a decade ago. By 2026, it is a regulatory fact, and it forces researchers, formulators, and science communicators to rethink how they compare oral delivery formats, gastric stability profiles, and pharmacokinetic exposure data across very different molecule classes. This article addresses GLP-1 Pills and Research-Use Peptides: How to Compare Oral Delivery, Gastric Stability, and Exposure Without Making Clinical Claims by focusing on formulation science variables, protease vulnerability, food effects, gastric emptying dynamics, and PK sampling frameworks rather than therapeutic outcomes.

Key Takeaways

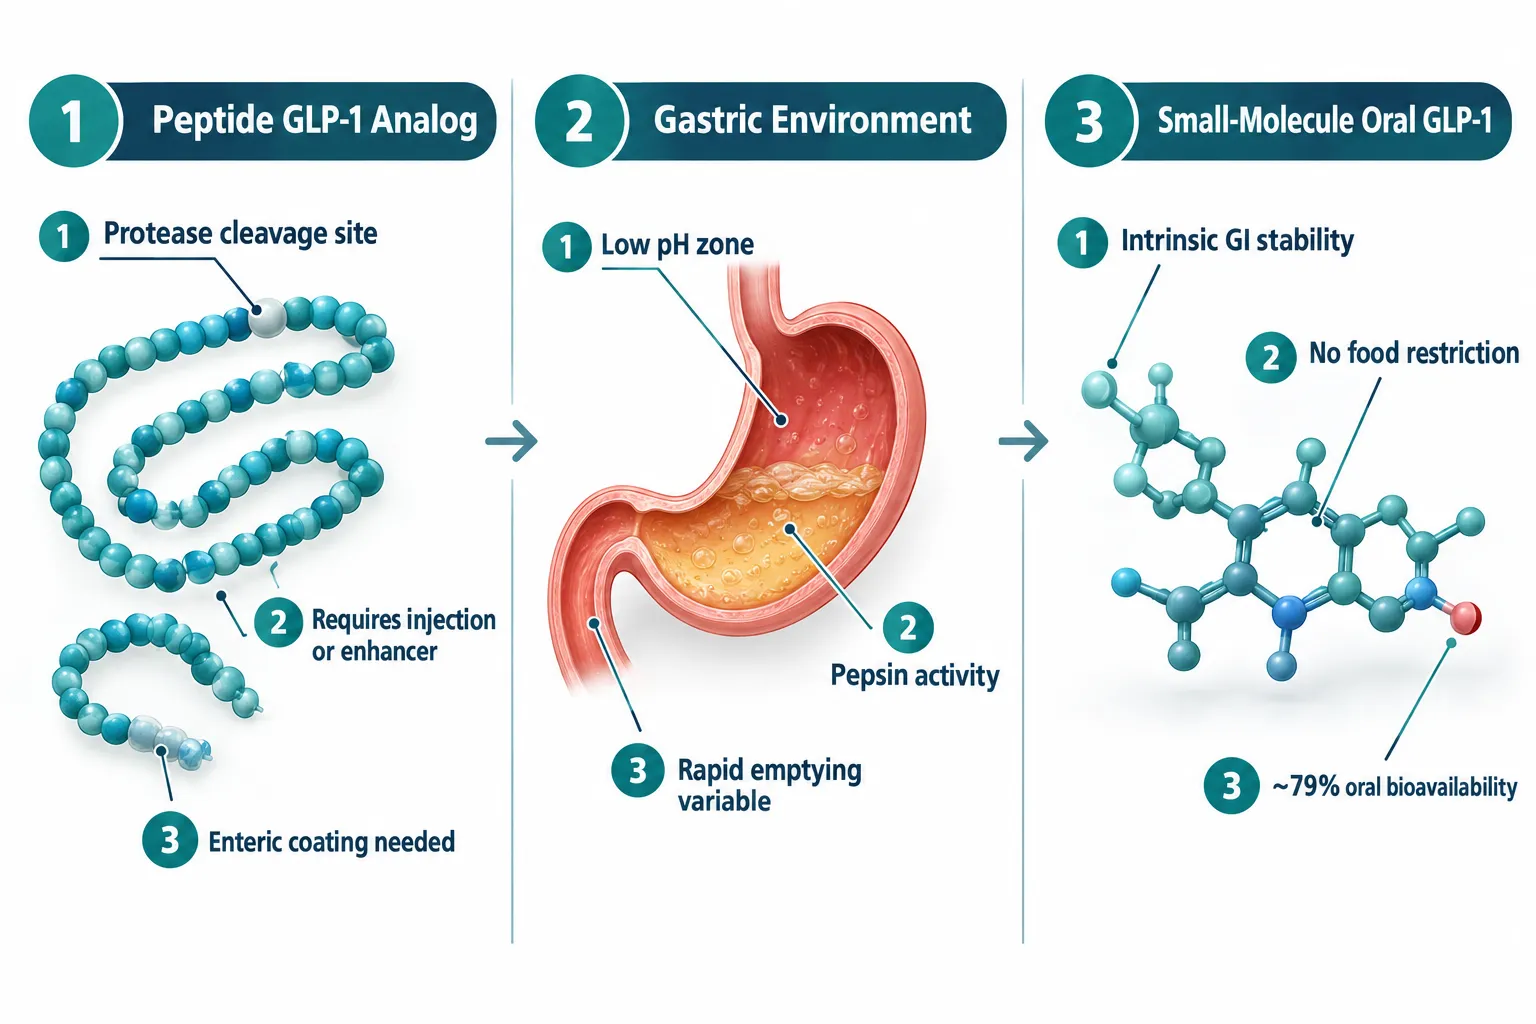
  • Small-molecule oral GLP-1 agonists achieve high oral bioavailability by bypassing the protease sensitivity that limits peptide GLP-1 analogs in the gastrointestinal tract.
  • Gastric pH, protease activity, and gastric emptying rate are the three primary stability variables that distinguish oral delivery performance between molecule classes.
  • Validated pharmacokinetic metrics, bioavailability, area under the curve (AUC), maximum concentration (Cmax), and half-life, provide a non-clinical framework for comparing exposure without making outcome claims.
  • Research-use peptides typically lack oral PK data, validated GI stability studies, and regulatory-grade impurity profiling, creating a measurable documentation gap versus approved oral GLP-1 tablets.
  • Non-clinical comparisons should anchor to formulation class, receptor pharmacology, dosing conditions, and quantified early-phase exposure metrics, not efficacy or safety endpoints.

The Formulation Science Behind Oral GLP-1 Delivery

The Formulation Science Behind Oral GLP-1 Delivery

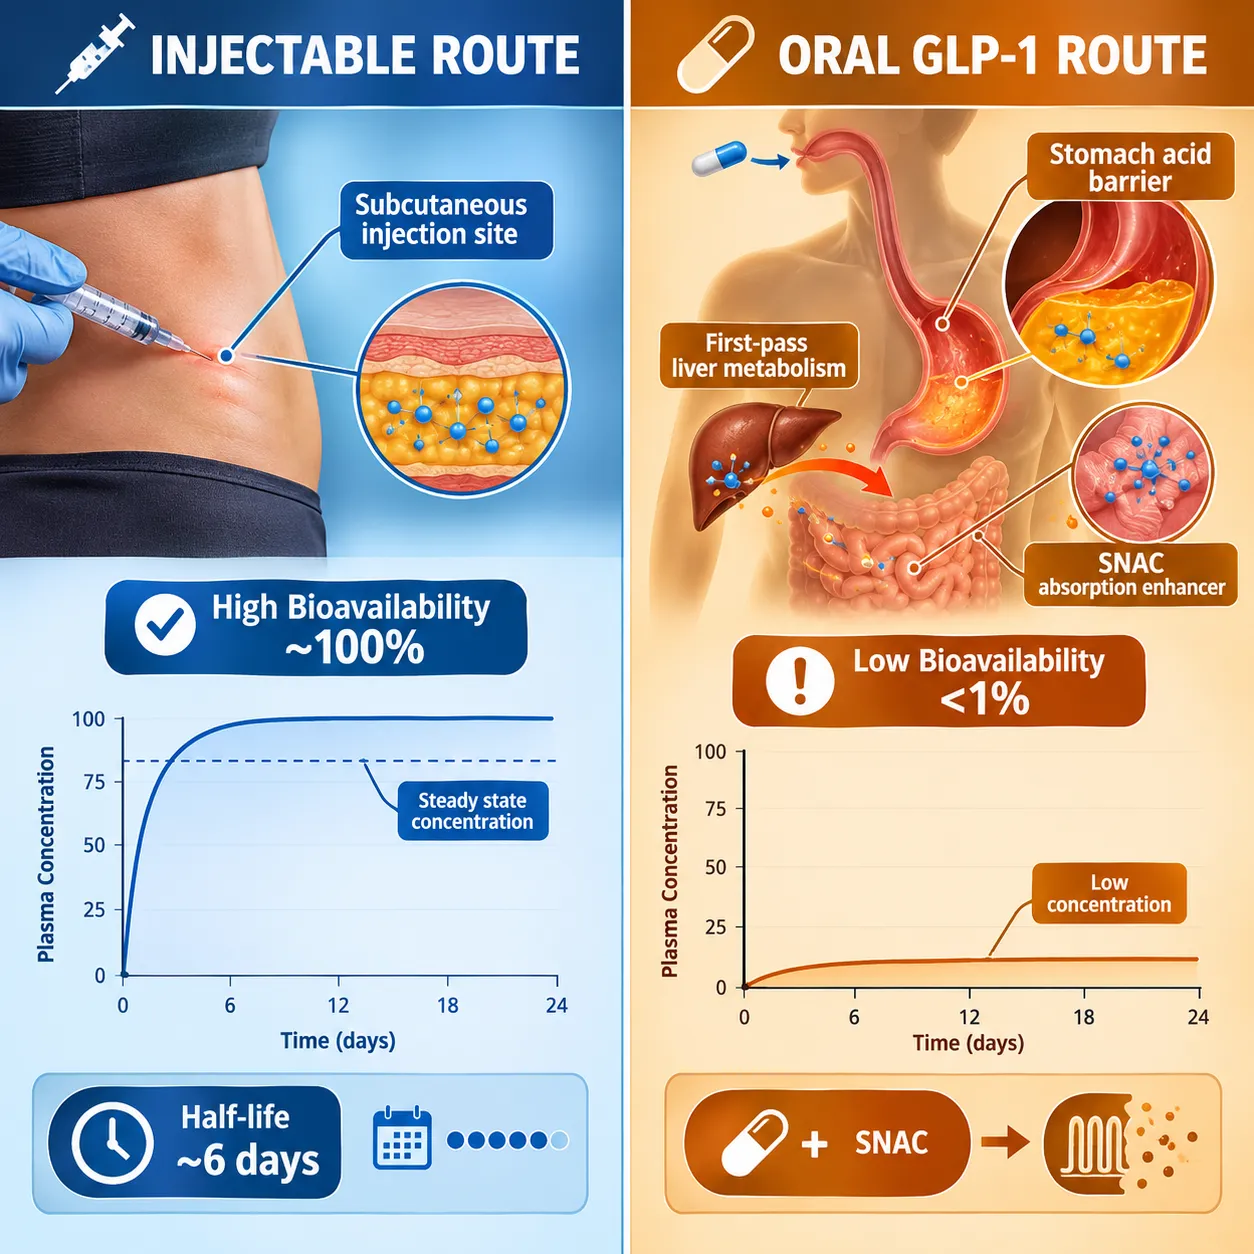
Peptide-based GLP-1 analogs face a fundamental barrier in the gastrointestinal tract: proteolytic enzymes. Pepsin in the stomach and endopeptidases in the small intestine cleave amide bonds in peptide chains rapidly and non-selectively. This is not a minor inconvenience, it is the primary reason injectable formulations became the standard route for GLP-1 receptor agonists for years.

Oral peptide GLP-1 formulations have addressed this through absorption enhancers (such as sodium N-[8-(2-hydroxybenzoyl)amino]caprylate, or SNAC) that create a localized pH shift near the gastric mucosa to reduce enzyme activity and promote transcellular absorption. This approach works, but it imposes strict administration conditions: a small volume of water, a fasting state of at least 30 minutes before and after dosing, and consistent gastric emptying timing.

The key delivery variables for any oral peptide GLP-1 formulation include:

  • Gastric pH at time of dosing (fasted vs. fed state alters acid secretion and enzyme concentration)
  • Gastric emptying rate (accelerated emptying reduces contact time with the absorptive enhancer)
  • Luminal protease concentration (varies with meal composition and timing)
  • Mucosal permeability at the absorption window

Small-molecule oral GLP-1 receptor agonists, such as orforglipron (approved in the U.S. and recommended by the European Medicines Agency in October 2026 under the name Foundayo), sidestep this framework entirely. Because the molecule is not a peptide, it has no amide bonds susceptible to pepsin or trypsin cleavage. It can be taken once daily without food or water restrictions, at any time of day, in a standard tablet formulation. This is not a convenience feature alone, it is a direct pharmacokinetic consequence of intrinsic GI stability.

"Intrinsic GI stability is a formulation outcome, not just a convenience variable, it determines whether exposure metrics gathered in fasted subjects translate to real-world dosing scenarios."

For those working in adjacent areas of peptide research, the BPC-157 core peptides documentation first research guide illustrates how formulation and stability documentation requirements apply across different peptide classes.


Comparing Research-Use Peptides Against Approved Oral GLP-1 Pills: A Non-Clinical Framework

Comparing Research-Use Peptides Against Approved Oral GLP-1 Pills: A Non-Clinical Framework

When comparing GLP-1 Pills and Research-Use Peptides: How to Compare Oral Delivery, Gastric Stability, and Exposure Without Making Clinical Claims, the most defensible structure anchors to five documented axes rather than outcome data:

Comparison Axis Approved Oral GLP-1 Pill Research-Use GLP-1 Peptide
Molecule class Small molecule, non-peptide Peptide analog
Oral bioavailability ~79% (documented, Phase 1/3) Not validated for oral route
GI stability testing Intrinsic, no enhancer needed Typically absent or unpublished
Dosing conditions No food or water restrictions Fasting required (if oral attempted)
Regulatory documentation Full label, impurity profile "Not for human use," no label

This table represents a formulation-science comparison, not a clinical one. No efficacy or safety claims are embedded in these axes. Researchers communicating about peptide receptor pharmacology, such as those studying GLP-3 peptide signaling pathway dynamics, can use this same axis structure to position their data without crossing into outcome language.

What research-use peptides commonly lack in oral delivery documentation:

  • Validated oral bioavailability data in any species
  • GI stability assays (simulated gastric fluid, simulated intestinal fluid)
  • Food-effect interaction studies
  • Defined AUC, Cmax, or effective half-life for oral administration
  • Regulatory-grade manufacturing certificates with impurity profiling

This is not a criticism of research-use compounds, it reflects their intended scope. Products categorized for in-vitro or preclinical laboratory use are not required to generate this data. However, the absence of this data defines the boundary of what can be stated. Related resources such as AOD-9604 sale research method notes, storage and traceability demonstrate how documentation-first approaches apply to research-grade peptides regardless of their mechanism of action.

For researchers exploring the emerging GLP-3 receptor space, the GLP-3 RT peptide and GLP-3R 30mg peptide GA9 product categories follow the same documentation gap framework, oral delivery variables remain uncharacterized at the research-grade level.


Using PK Metrics to Structure Exposure Comparisons Without Clinical Language

Using PK Metrics to Structure Exposure Comparisons Without Clinical Language

Pharmacokinetic parameters are the bridge between formulation science and non-clinical exposure comparison. They describe what a molecule does in a biological system without asserting what that means for health outcomes. This is precisely where GLP-1 Pills and Research-Use Peptides: How to Compare Oral Delivery, Gastric Stability, and Exposure Without Making Clinical Claims becomes a practical communication skill rather than just a compliance exercise.

The four PK metrics most useful for non-clinical oral delivery comparison are:

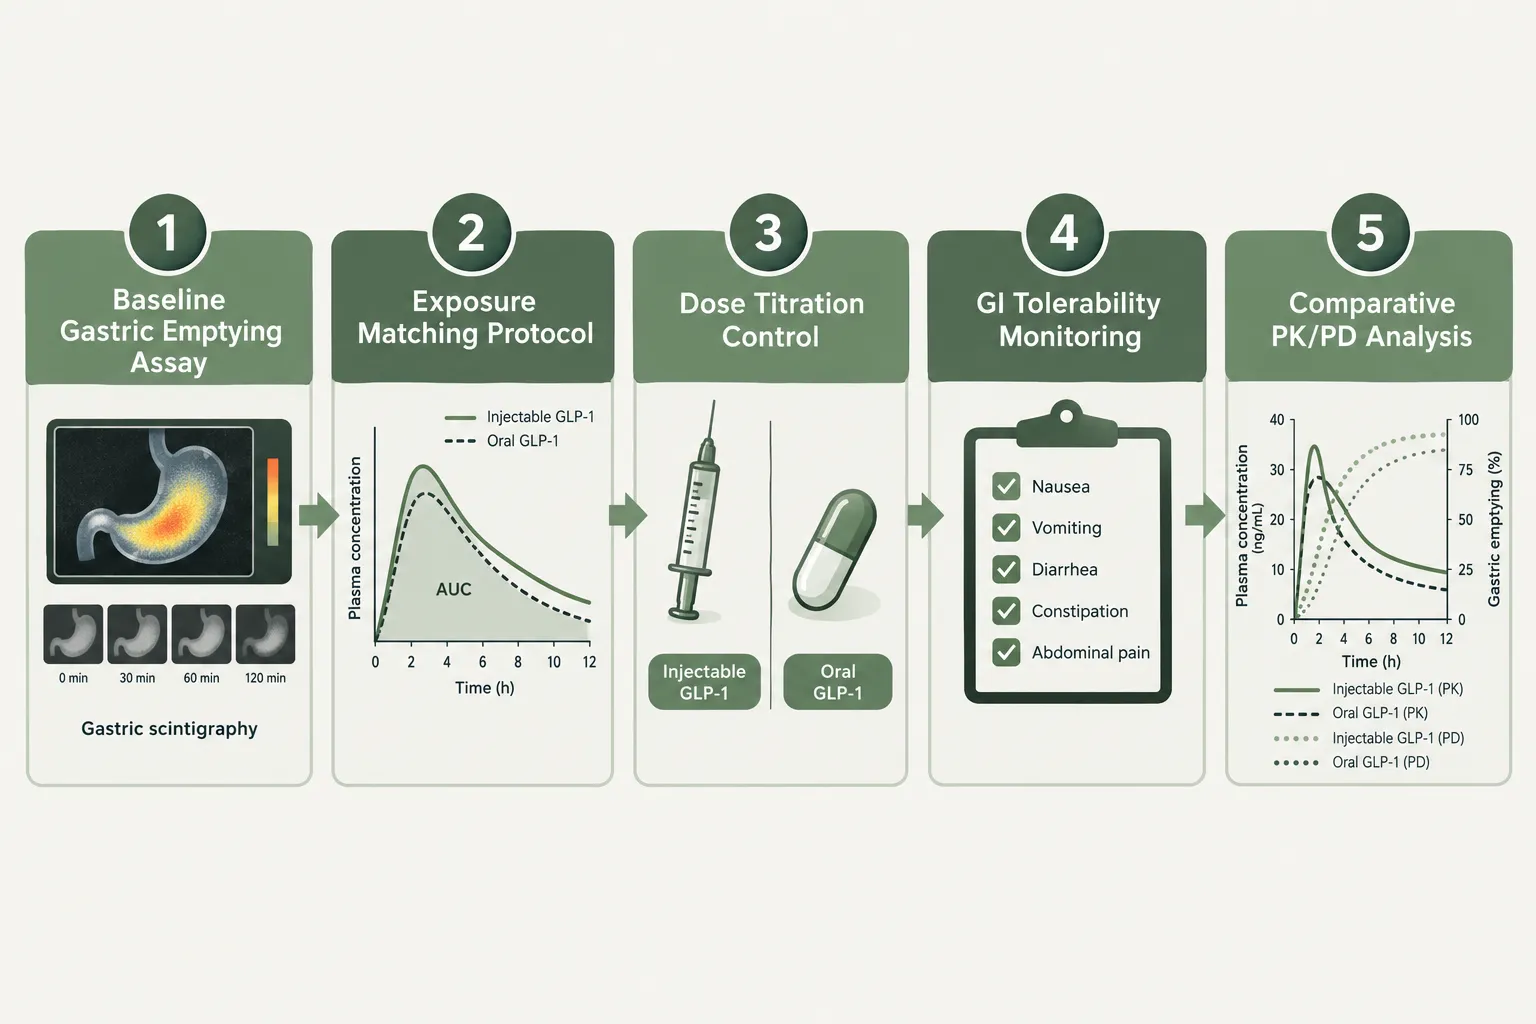
  1. Oral bioavailability (F%), the fraction of the administered dose reaching systemic circulation. For orforglipron, this is approximately 79%. For research-use peptide GLP-1 analogs administered orally, this value is typically undefined.
  2. Maximum concentration (Cmax), the peak plasma concentration after a single dose. Relevant for understanding receptor occupancy windows without invoking pharmacodynamic outcomes.
  3. Area under the curve (AUC), total drug exposure over time. A higher AUC from an oral route indicates better absorption relative to the administered dose.
  4. Effective half-life (t½), how long the molecule maintains relevant plasma concentrations. Orforglipron sustains receptor activation over approximately 24 hours, supporting once-daily dosing.

When describing an oral GLP-1 research peptide, the absence of documented AUC or half-life data is itself a meaningful statement. It means exposure cannot be characterized, not that exposure does not occur.

The Phase 3 program for orforglipron generated detailed dose-response and exposure-response data over 72 weeks and beyond, including a 52-week study evaluating oral GLP-1 as a maintenance-phase agent following prior injectable GLP-1 or GIP/GLP-1 agonist therapy. That depth of PK characterization is the standard against which research-use peptide documentation can be benchmarked. Researchers interested in peptide characterization standards may also find the cagrilinitide peptide for sale category relevant as a dual-agonist research comparator requiring similar PK framing.

For pipeline discussion, any new small-molecule or peptide oral GLP-1 candidate should be explicitly labeled as carrying unproven exposure characteristics until Phase 1 PK data are published. Orforglipron demonstrates that non-peptide design, robust GI stability, and well-characterized oral exposure are achievable, but that does not transfer automatically to structurally distinct candidates.

Those working with injectable research peptides can reference related characterization approaches in the SS-31 10mg research peptide considerations documentation as a model for how PK and stability variables are framed in non-clinical contexts.


Conclusion

The comparison between oral GLP-1 pills and research-use peptides is most credible, and most useful, when it is built on formulation variables, not outcome variables. Three actionable steps apply immediately:

  1. Anchor every oral delivery comparison to documented axes: molecule class, GI stability mechanism, dosing conditions, oral bioavailability, and PK profile. Where data are absent, state the absence explicitly rather than inferring equivalence.
  2. Use PK metrics as the non-clinical language of exposure: Cmax, AUC, bioavailability, and half-life describe what a molecule does pharmacokinetically without asserting what it achieves clinically. This language is defensible, precise, and appropriate for research-use contexts.
  3. Treat regulatory documentation as a benchmark, not a ceiling: The approval of an oral GLP-1 pill with a full regulatory label and validated oral bioavailability sets a documentation standard. Research-use peptides can be positioned honestly against that standard by identifying which data exist, which are pending, and which have not been generated.

Gastric stability is not an abstract concept, it determines whether a molecule survives long enough in the GI tract to reach an absorptive surface. Framing oral delivery comparisons around that physical reality, rather than clinical outcomes, keeps the science rigorous and the communication compliant.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/glp-1-pills-and-research-use-peptides-how-to-compare-oral-delivery-gastric-stabi.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-23 13:04:192026-10-23 13:04:19GLP-1 Pills and Research-Use Peptides: How to Compare Oral Delivery, Gastric Stability, and Exposure Without Making Clinical Claims
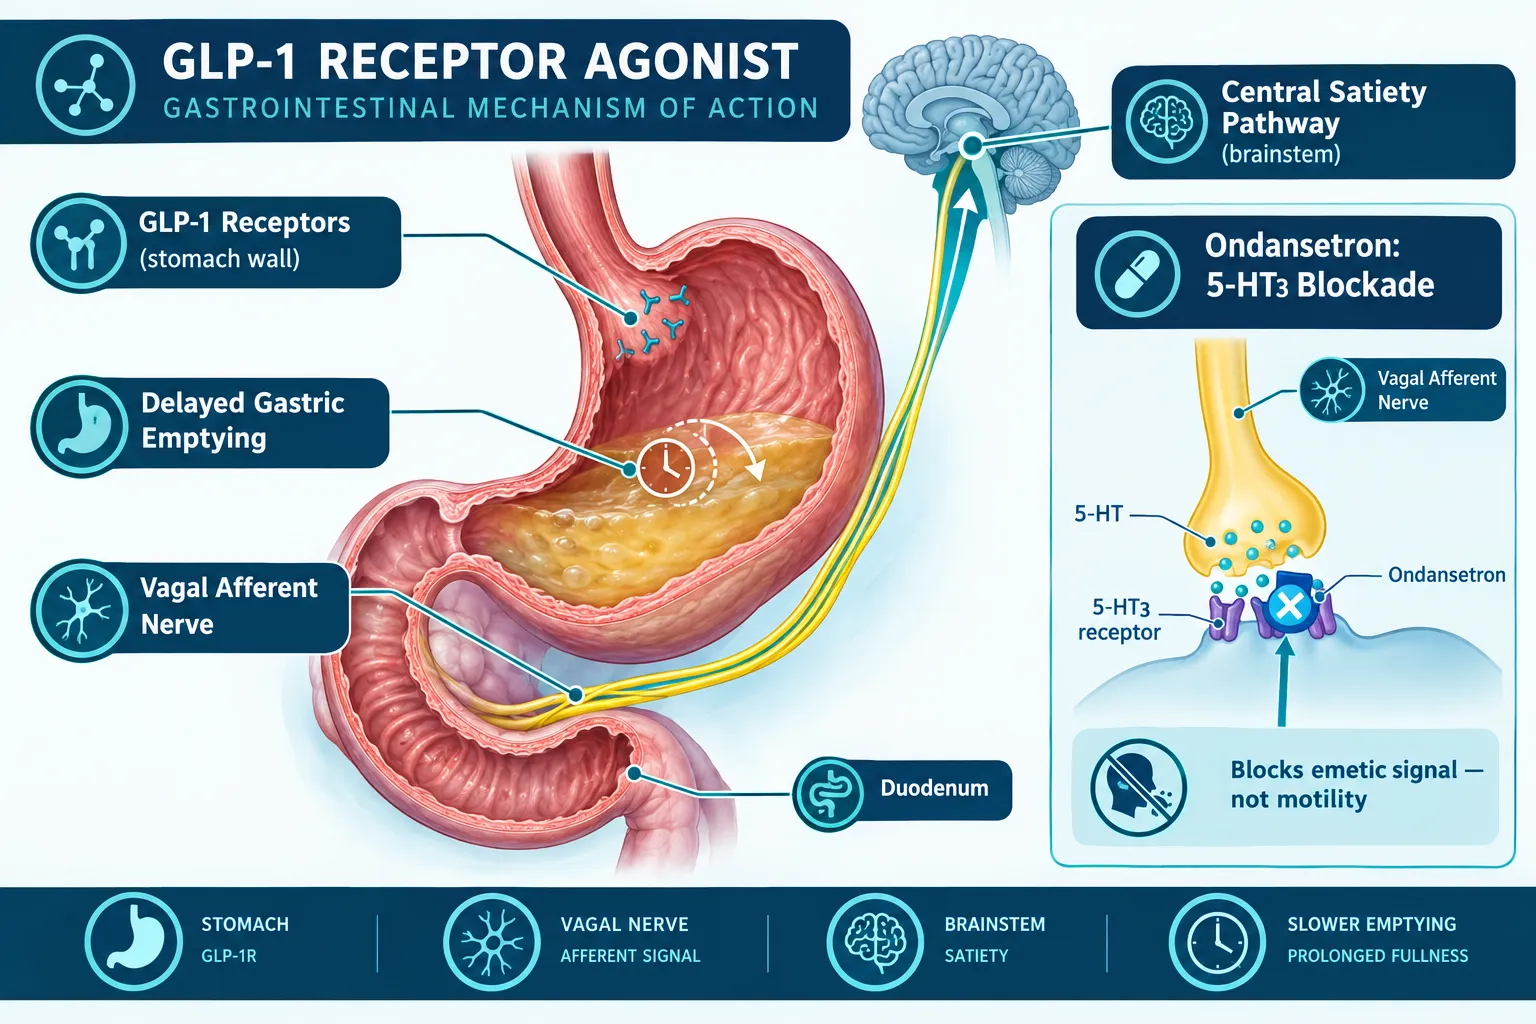
Omeprazole, Famotidine, and Ondansetron: A Medication-Confounder Matrix for GLP and GLP-2 Research

Omeprazole, Famotidine, and Ondansetron: A Medication-Confounder Matrix for GLP and GLP-2 Research

October 22, 2026/0 Comments/in Uncategorized/by

More than half of patients starting a GLP-1 receptor agonist will be co-prescribed an acid-suppressive or antiemetic drug within the first ninety days, yet most published GLP-1 and GLP-2 studies treat that co-prescription as background noise rather than a mechanistic variable. The result is a quiet but serious problem of confounding. This article maps how omeprazole, famotidine, and ondansetron alter gastric emptying, intragastric pH, serotonin signaling, and nutrient absorption in ways that directly intersect with incretin biology, and explains why building a formal medication-confounder matrix for GLP and GLP-2 research is no longer optional.

Key Takeaways

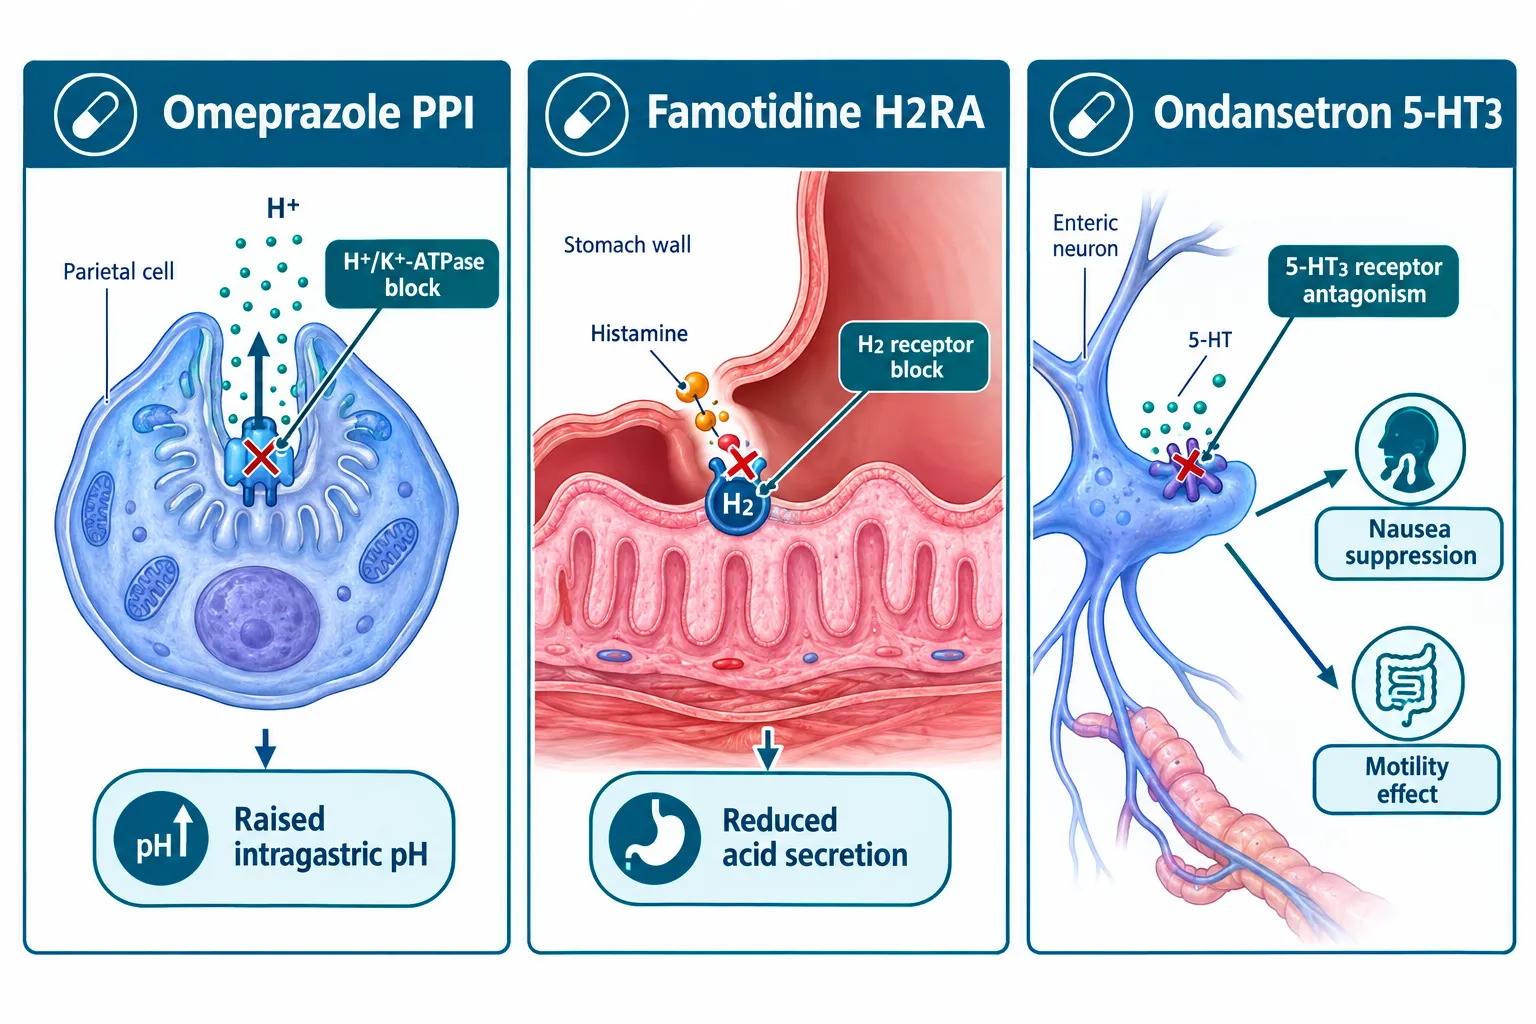
  • Omeprazole and famotidine raise intragastric pH by blocking separate steps in acid secretion, which can alter oral GLP-1 absorption timing and endogenous incretin responses linked to gastric pH.
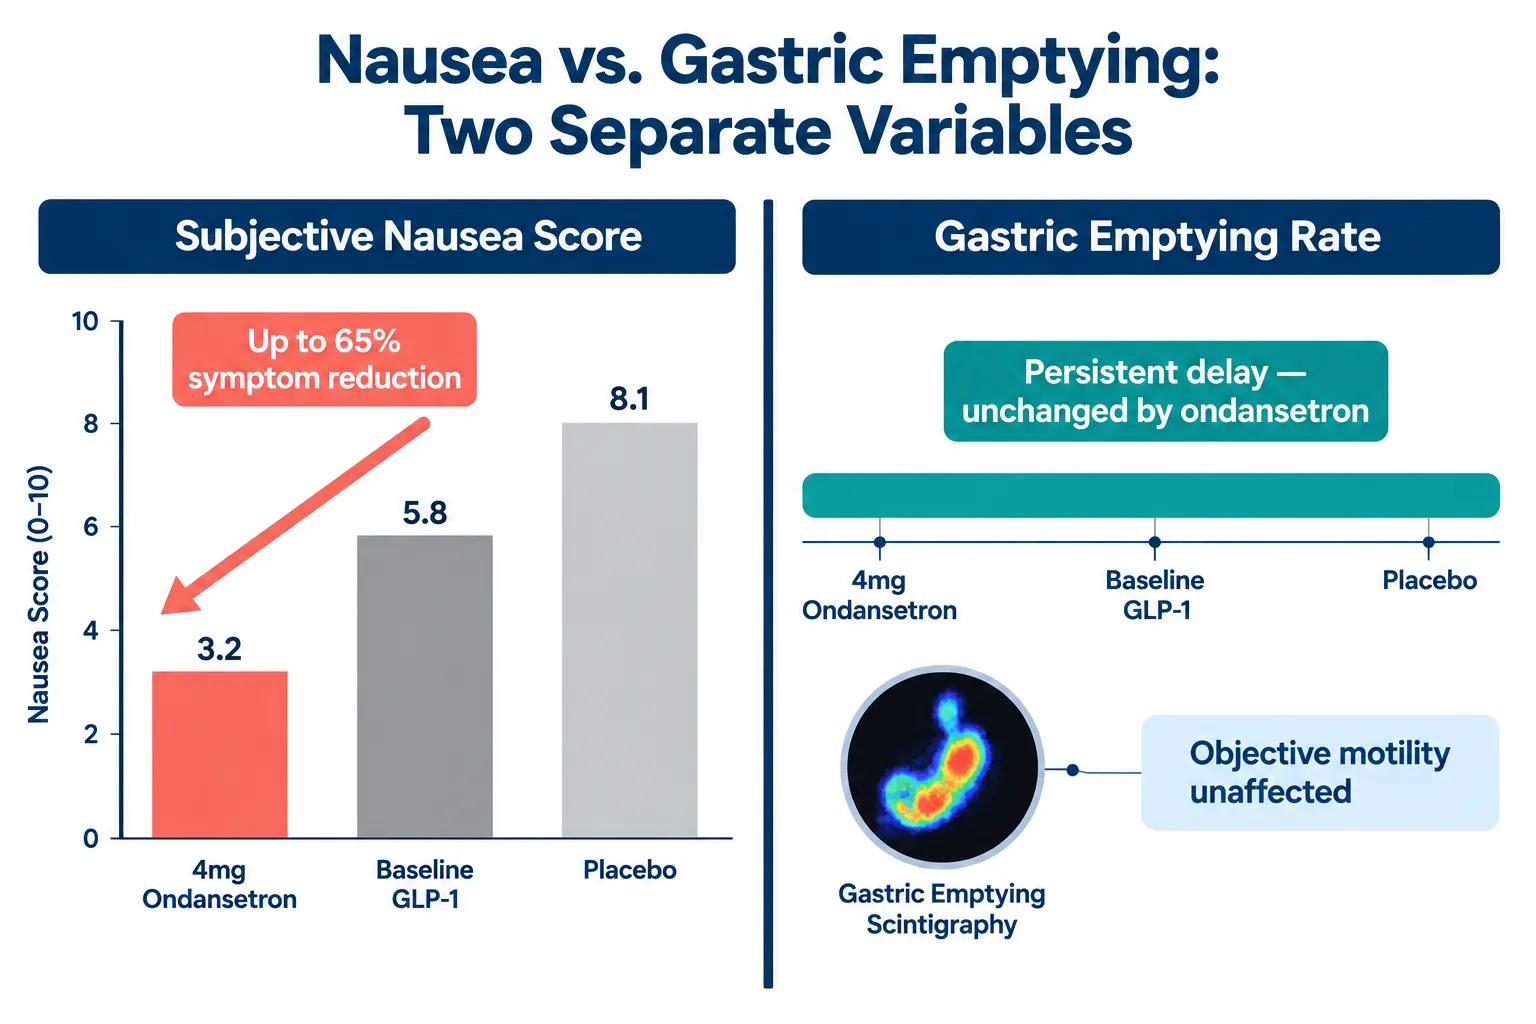
  • Ondansetron suppresses nausea via 5-HT3 receptor antagonism, but this same pathway influences gut motility and intestinal permeability, both endpoints commonly tracked in GLP-2 research.
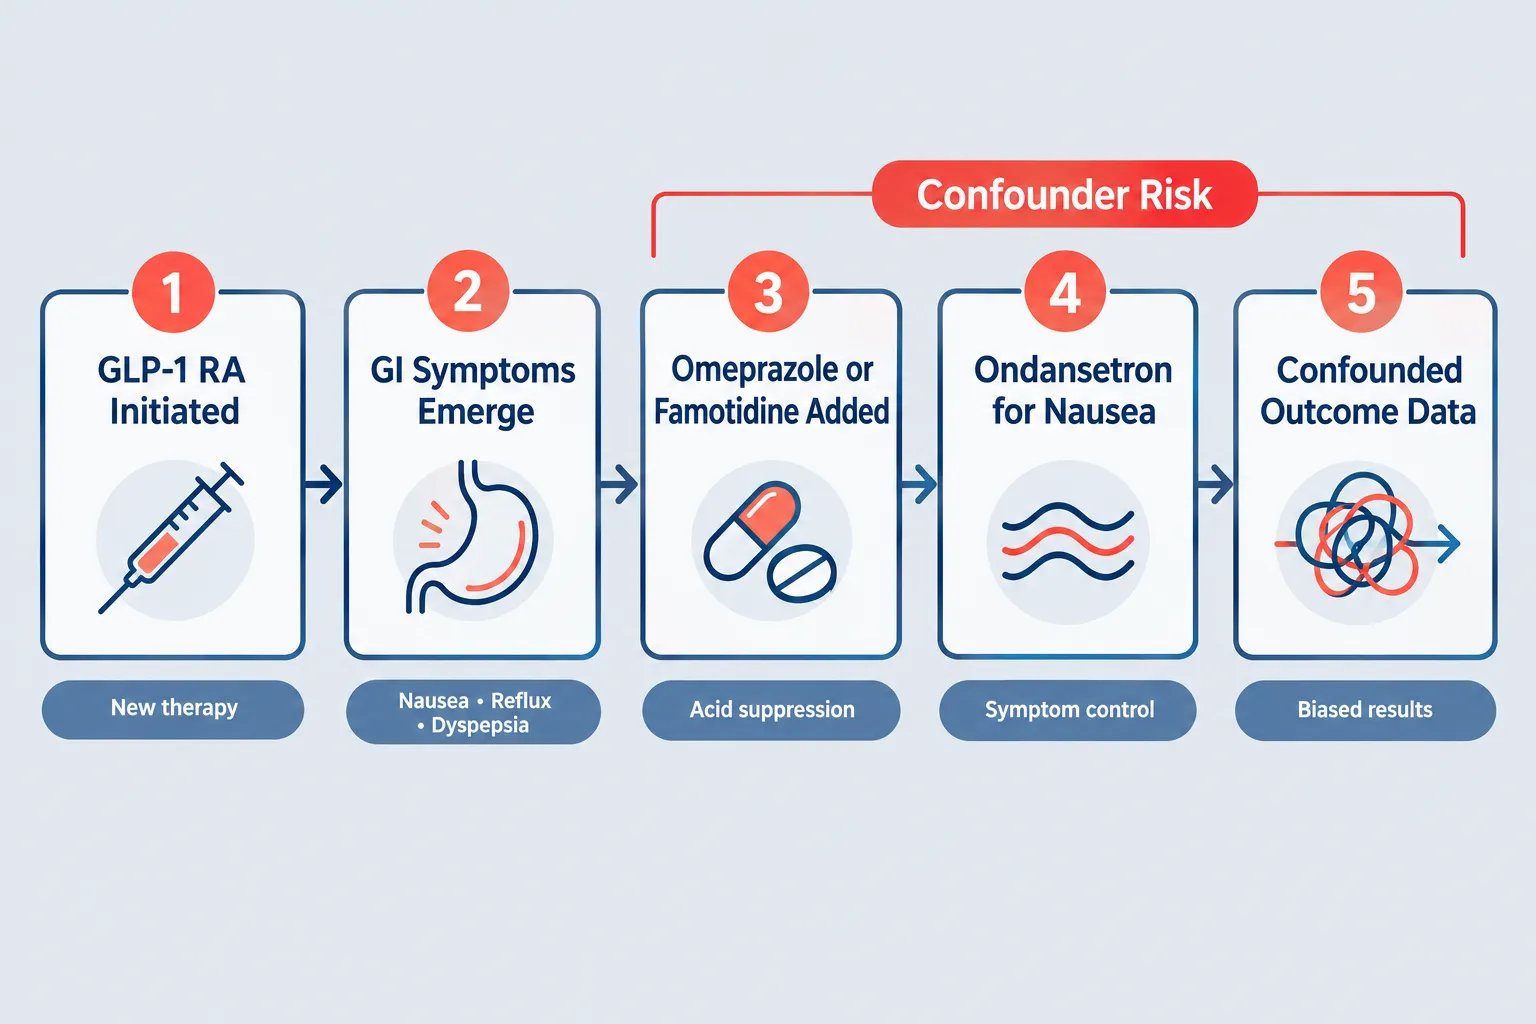
  • Because these medications are disproportionately prescribed to patients with the worst GI symptoms, their use is not random; it is indication-driven, creating classic confounding by indication.
  • Gastric emptying, nutrient transit, symptom scores, and even cardiometabolic endpoints can shift in response to the co-medications rather than the incretin agent alone.
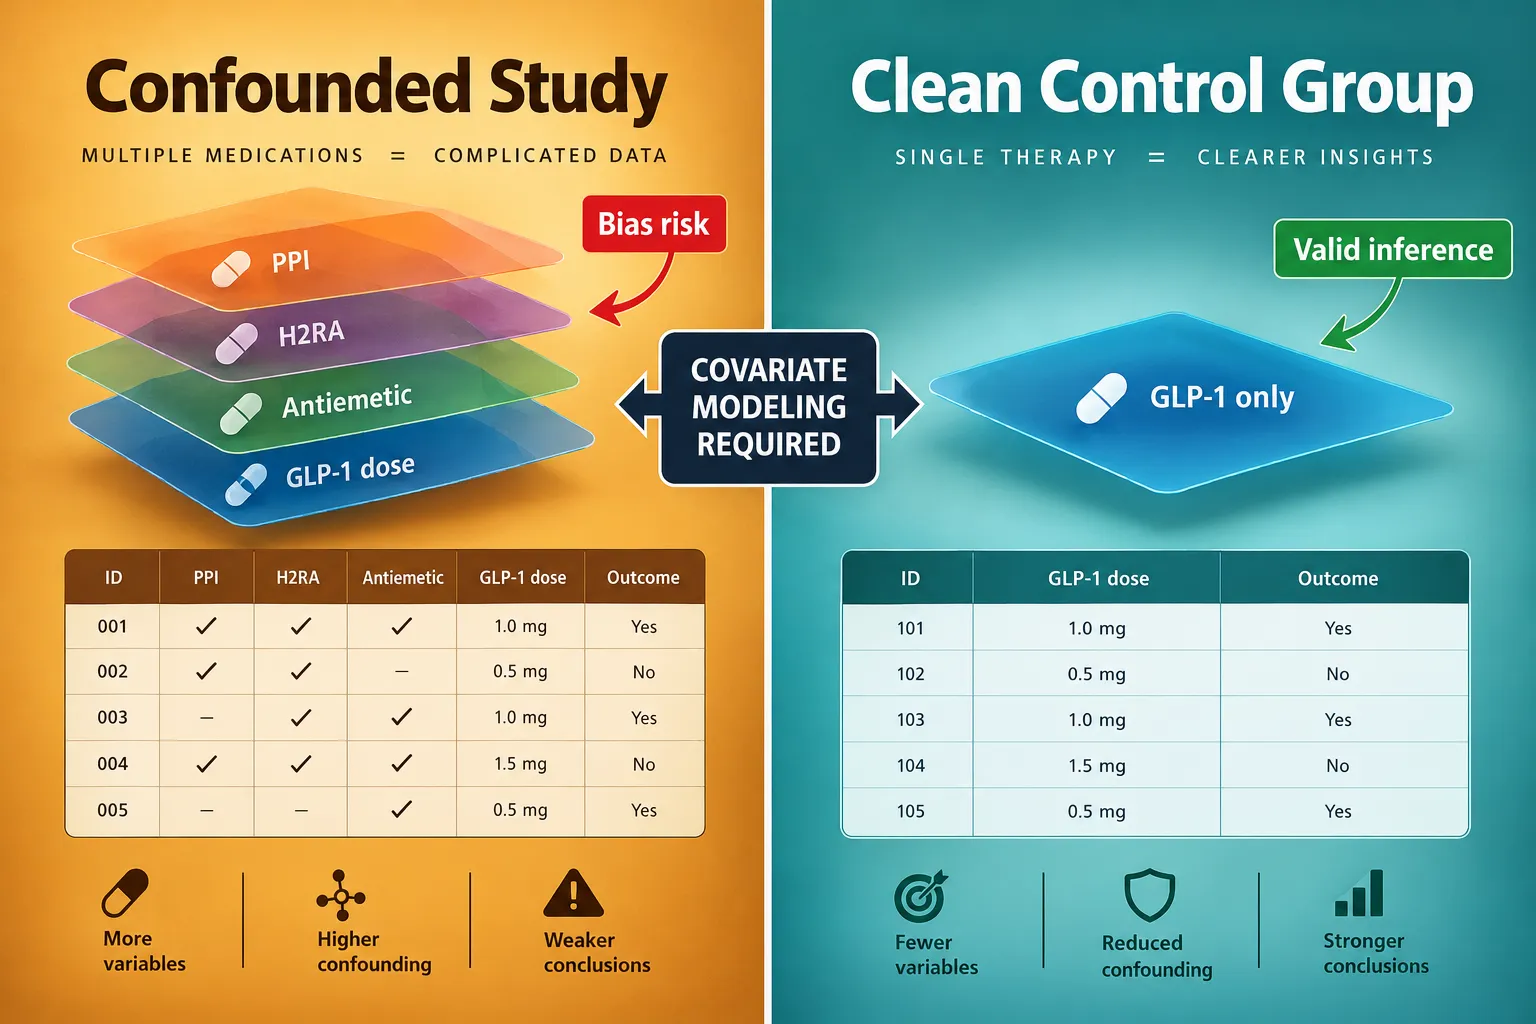
  • Selecting clean control groups, subjects without acid-suppressive or antiemetic therapy, and modeling these drugs as explicit covariates are the two most impactful design choices for valid inference.

Why the Medication-Confounder Matrix Matters for GLP and GLP-2 Research

Why the Medication-Confounder Matrix Matters for GLP and GLP-2 Research

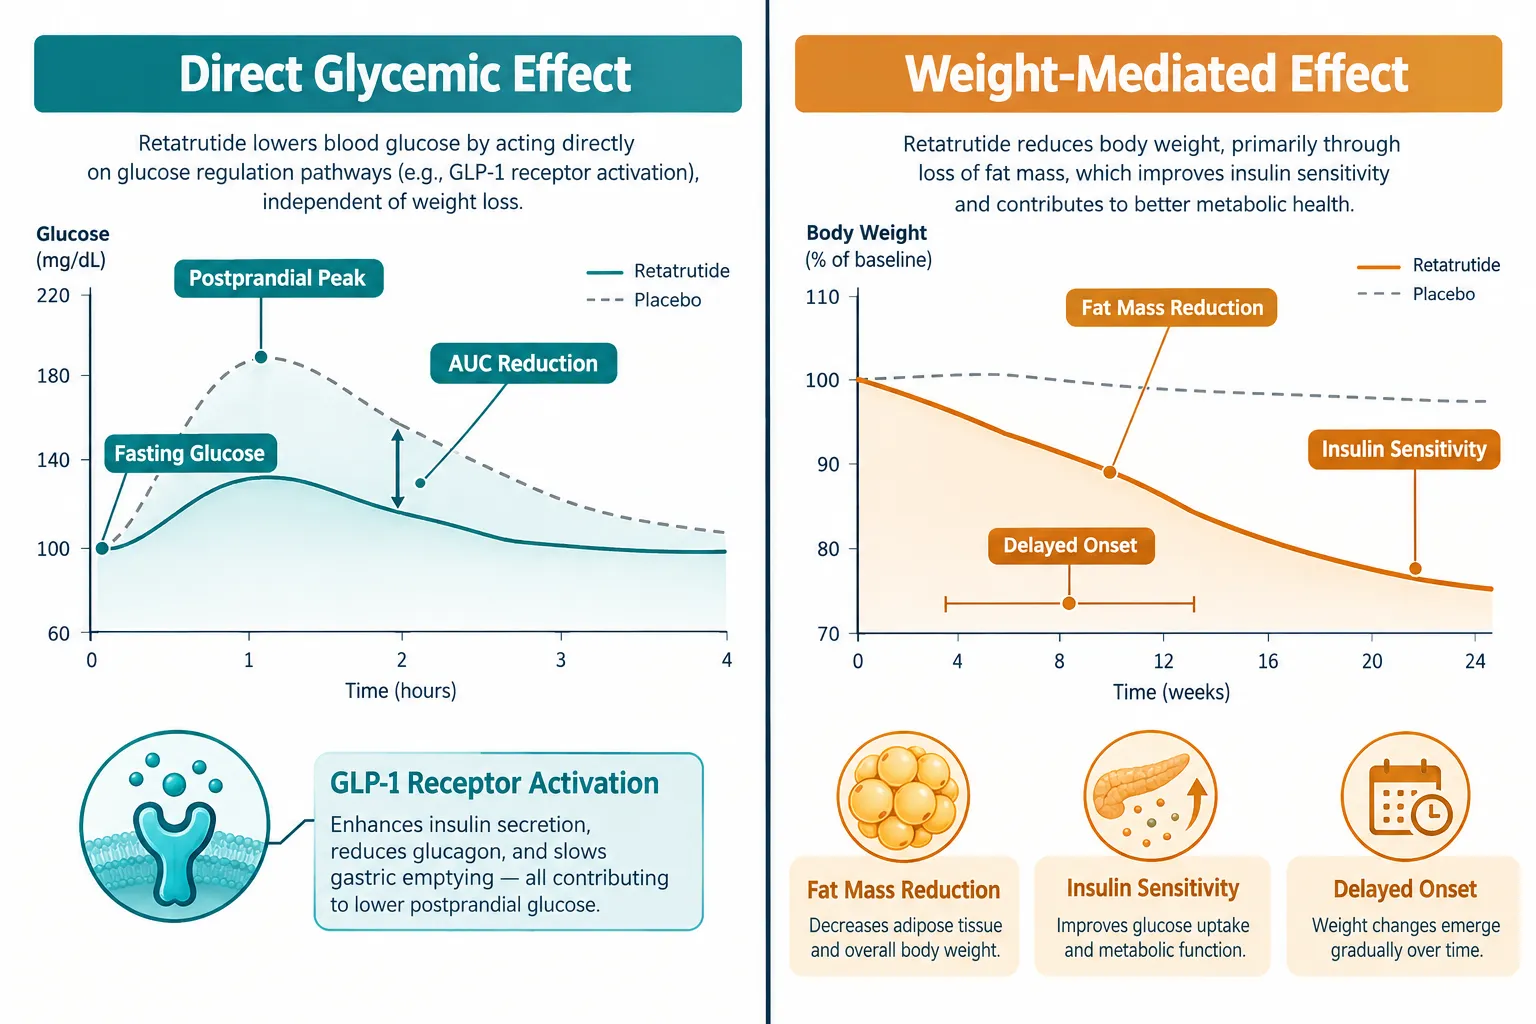
GLP-1 receptor agonists work through several overlapping mechanisms: stimulating glucose-dependent insulin release, suppressing glucagon, slowing gastric emptying, and reducing appetite. GLP-2 analogues primarily target intestinal mucosal growth and permeability. Both pathways sit at the intersection of gastric acid physiology and gut motility, exactly where omeprazole, famotidine, and ondansetron exert their effects.

Omeprazole, a proton-pump inhibitor (PPI), irreversibly inhibits the parietal-cell H+/K+-ATPase enzyme, substantially raising intragastric pH. Famotidine, an H2-receptor antagonist (H2RA), blocks histamine H2 receptors upstream of the same proton pump, producing a more moderate and reversible acid suppression. Both drugs therefore alter the stomach's chemical environment in ways that affect oral peptide stability, nutrient-triggered GLP-1 secretion from L-cells, and the symptom landscape that researchers use to measure tolerability.

Ondansetron acts as a 5-HT3 antagonist. Its antiemetic action blocks serotonin-mediated signaling in both the gut wall and the central chemoreceptor trigger zone. Because intestinal serotonin is a key regulator of peristalsis and mucosal secretion, chronic ondansetron use can slow colonic transit and subtly modify intestinal permeability, endpoints that appear directly in GLP-2 efficacy models.

For researchers exploring GLP-3 peptide signaling pathways or reviewing peptides 101 fundamentals including GLP mechanisms, understanding these pharmacological overlaps is foundational.


How Each Drug Creates Confounding in GLP and GLP-2 Studies

How Each Drug Creates Confounding in GLP and GLP-2 Studies

The confounding structure for omeprazole, famotidine, and ondansetron in GLP and GLP-2 research is not random. It is driven by indication, sicker patients with more severe GI intolerance are more likely to receive all three. This table summarizes each drug's primary mechanism, the research endpoints it can distort, and the direction of bias when the drug is ignored.

Drug Mechanism Endpoints Affected Direction of Potential Bias
Omeprazole H+/K+-ATPase inhibition, raises pH Oral GLP-1 absorption, L-cell secretion, gastric emptying Overestimates tolerability in treated groups
Famotidine H2 receptor block, reduces acidity Nutrient-triggered incretin response, reflux symptom scores Masks true GI burden; inflates tolerability comparisons
Ondansetron 5-HT3 antagonism, suppresses nausea Motility, permeability, nausea/vomiting endpoints Attenuates GI signal; confounds discontinuation analysis

Gastric pH and Oral GLP-1 Pharmacokinetics

Clinical trials of oral semaglutide found no significant pharmacokinetic drug-drug interaction with standard-dose omeprazole, which is reassuring. However, timing remains a practical confounder in real-world effectiveness studies: taking omeprazole or famotidine too close to an oral GLP-1 tablet can reduce absorption. In observational data where medication timing is rarely recorded, this creates unmeasured variability that inflates outcome variance and can mask true effects.

Gastric Emptying and GLP-1-Induced Gastroparesis

A significant body of 2026 research confirms that GLP-1 receptor agonists can induce or exacerbate gastroparesis through their pharmacologic slowing of gastric motility. Clinicians frequently respond by adding PPIs, H2 blockers, and antiemetics. This creates a cascade: GLP-1 slows gastric emptying, which drives PPI and antiemetic prescribing, which in turn modifies subsequent gastric emptying measurements, nutrient transit scores, and symptom outcomes. Any study that does not model this cascade will misattribute combined drug effects to the GLP-1 or GLP-2 agent alone.

Long-Term PPI Use and Secondary Endpoints

Long-term omeprazole use carries observational associations with enteric infections, micronutrient deficiencies (magnesium, vitamin B12), osteoporotic fractures, chronic kidney disease, and gastrointestinal cancers, though causality is unproven and many signals are themselves confounded. When GLP-1 or GLP-2 trials track cardiometabolic, renal, bone, or cancer endpoints over months to years, failure to adjust for chronic PPI exposure risks misattributing PPI-related events to the incretin therapy under study.

Building a Clean Confounder Matrix: Study Design Recommendations

Building a Clean Confounder Matrix: Study Design Recommendations

The practical goal is not to eliminate all co-medication use, that is clinically unrealistic, but to model it explicitly and to define clean control groups for sensitivity analyses. Advanced pharmacoepidemiologic studies of GLP-1 receptor agonists now routinely include antiemetic and acid-suppressive drug exposure in propensity-score models and fine-stratification weighting, demonstrating that the field already recognizes these as meaningful covariates.

Researchers working with GLP and GLP-2 compounds, including those reviewing GLP-1 peptide product considerations or evaluating GLP-3 receptor peptide options, should integrate the following design practices:

1. Define the confounder matrix at protocol stage

List omeprazole, famotidine, ondansetron, and other relevant co-medications as pre-specified covariates before data collection begins. Include both prevalence (ever-use) and timing (days from index date) as separate variables.

2. Stratify by acid-suppressive use

Run primary analyses in the full cohort and in a sensitivity cohort restricted to subjects with no PPI or H2RA use. A difference in effect estimates between the two cohorts signals meaningful confounding.

3. Treat ondansetron as a severity proxy

Ondansetron prescribing closely tracks GLP-1-induced nausea severity. Including it as a time-varying covariate in outcome models captures disease-severity confounding that cannot be measured directly.
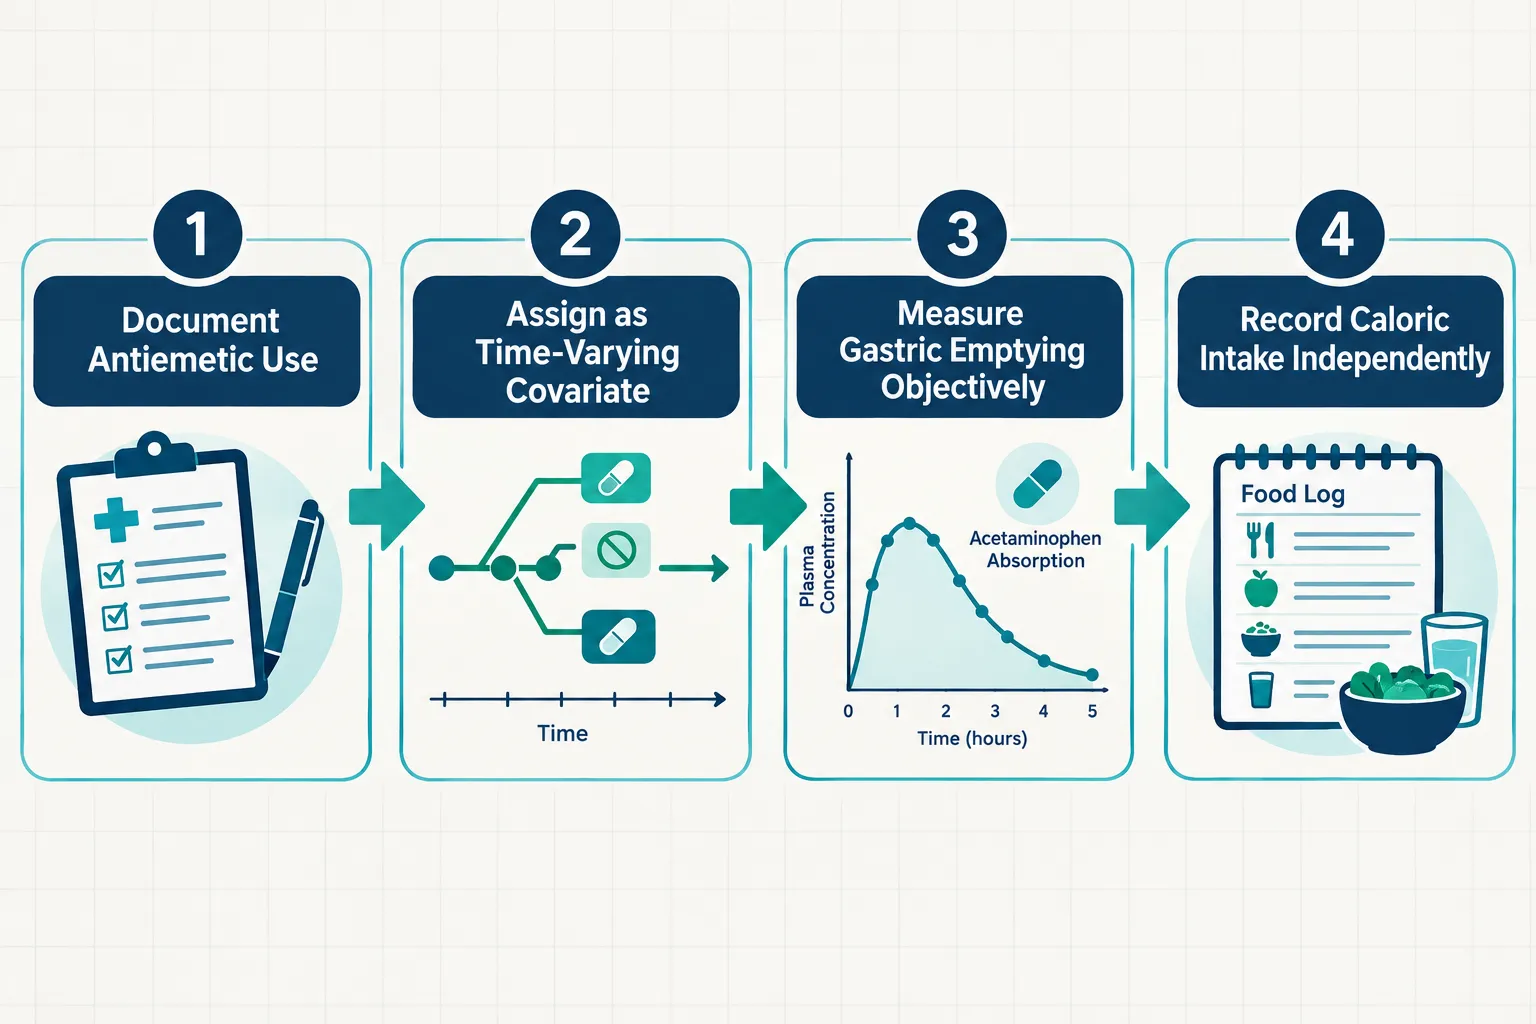
4. Separate symptom endpoints from motility endpoints

Nausea scores reflect both the GI burden of GLP-1 therapy and the suppressive effect of antiemetics. Gastric emptying time reflects both GLP-1 pharmacology and the motility effects of 5-HT3 blockade. Treating these as equivalent "GI outcome" measures collapses a critical distinction.

5. Record timing of co-medications relative to GLP doses

For oral GLP-1 research especially, the window between PPI/H2RA dosing and peptide administration is a source of absorption variability that can only be addressed if timing data are collected prospectively.

Historical precedent from pharmacoepidemiology, particularly from studies evaluating pneumonia risk with acid-suppressive therapy, shows that thorough covariate adjustment for PPI and H2RA use substantially changes estimated effect sizes. The same rigor is warranted in incretin research.

Researchers interested in related compound interactions may find value in the visceral fat research tag collection and in reviewing tesa peptide benefits, where co-medication confounding follows similar structural patterns.


Conclusion

The medication-confounder matrix for omeprazole, famotidine, and ondansetron in GLP and GLP-2 research is not a theoretical concern, it is an active source of bias in currently published literature. Each drug touches the gastric pH, motility, serotonin signaling, or absorption pathways that define GLP and GLP-2 study endpoints. Because all three are prescribed preferentially to patients with the most severe GI burden, their use encodes indication-driven confounding that simple covariate adjustment can miss if the matrix is not specified carefully.

Actionable next steps for research teams:

  • Add omeprazole, famotidine, and ondansetron as mandatory variables in all GLP-1 and GLP-2 observational protocols in 2026 and beyond.
  • Pre-register clean-control sensitivity analyses restricted to subjects with no acid-suppressive or antiemetic therapy.
  • Collect medication-timing data for oral GLP-1 studies, not just presence or absence of co-prescriptions.
  • Treat ondansetron use as both a confounder and a severity marker, adjusting for it as a time-varying covariate.
  • Report confounder-adjusted and unadjusted effect estimates side by side so readers can assess the magnitude of confounding in any given dataset.

Building this matrix from the start is far less expensive than correcting for it after data collection. Clean, well-specified studies produce evidence that survives scrutiny, and that ultimately advances the science of incretin and intestinal peptide research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/omeprazole-famotidine-and-ondansetron-a-medication-confounder-matrix-for-glp-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-22 13:04:452026-10-22 13:04:45Omeprazole, Famotidine, and Ondansetron: A Medication-Confounder Matrix for GLP and GLP-2 Research
Retatrutide Phase 3 Results for Sleep Apnea and Osteoarthritis: How Researchers Should Select Disease-Specific Endpoints

Retatrutide Phase 3 Results for Sleep Apnea and Osteoarthritis: How Researchers Should Select Disease-Specific Endpoints

October 21, 2026/0 Comments/in Uncategorized/by

A drug that cuts dangerous breathing pauses by more than 60 percent and slashes knee pain scores by nearly three-quarters, those are not typical weight-loss numbers. They are disease-specific signals, and they only appear when researchers choose the right endpoint from the start. The retatrutide Phase 3 results for sleep apnea and osteoarthritis: how researchers should select disease-specific endpoints is exactly the question that the TRIUMPH program answers in 2026, offering a practical blueprint for endpoint strategy across multi-system obesity-related conditions.

Key Takeaways

  • Retatrutide's TRIUMPH Phase 3 program met primary endpoints across obesity, obstructive sleep apnea (OSA), and knee osteoarthritis (OA) at approximately 80 weeks.
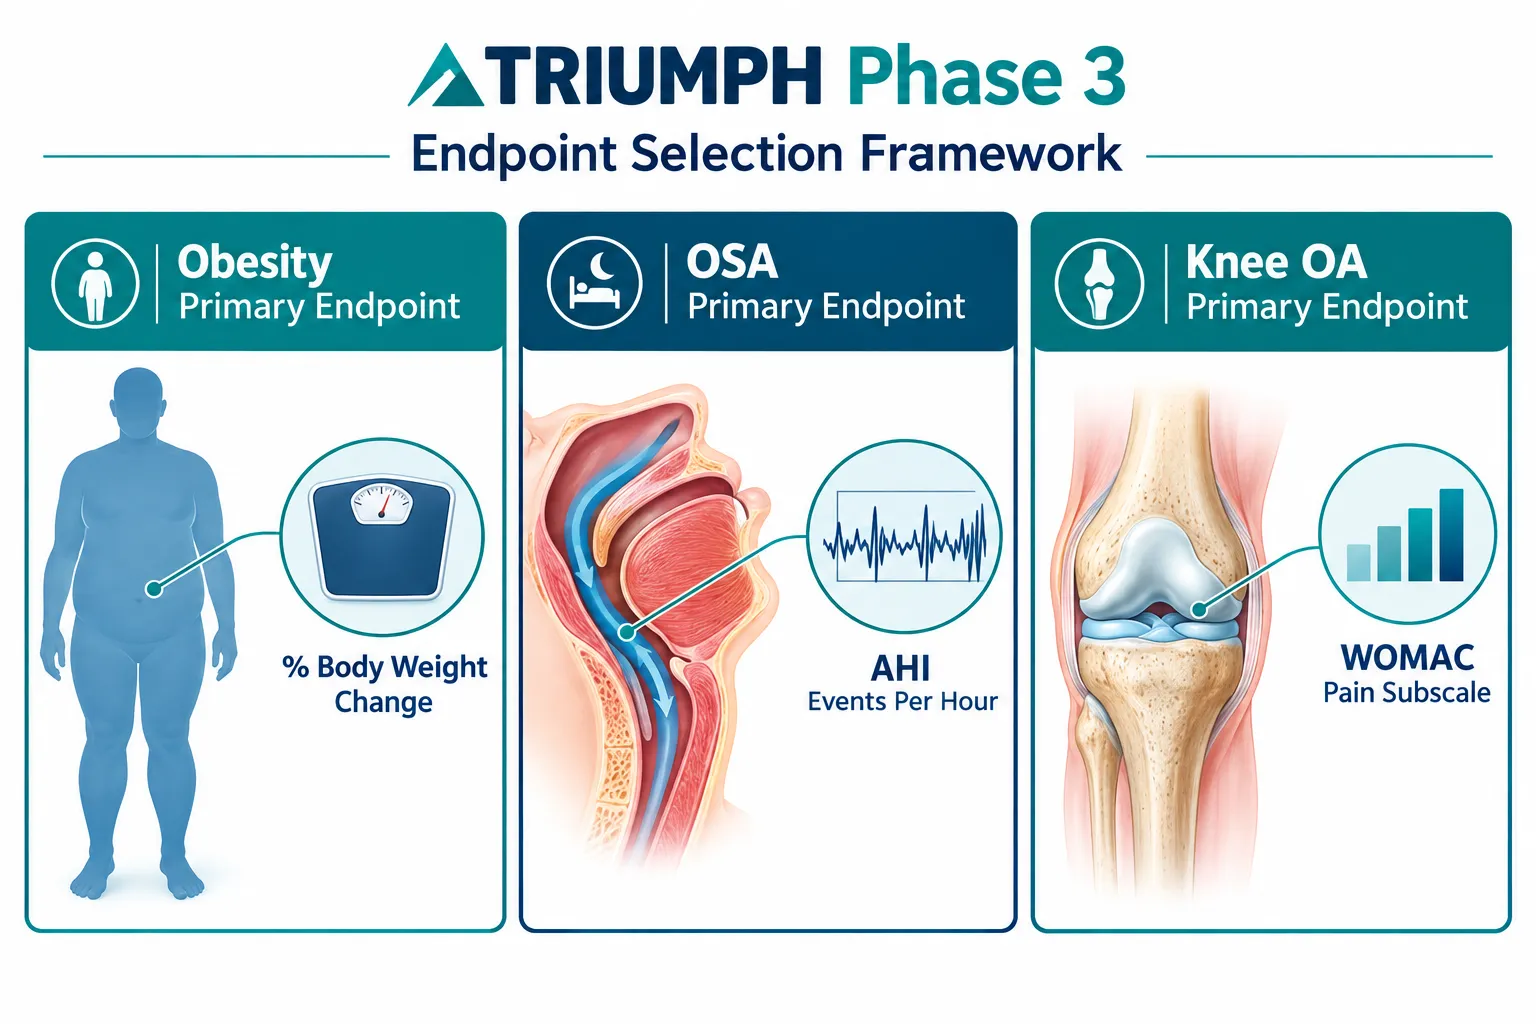
  • The Apnea-Hypopnea Index (AHI) and the WOMAC pain subscale were chosen as disease-specific primary endpoints for OSA and knee OA, respectively, capturing benefits that go beyond weight loss alone.
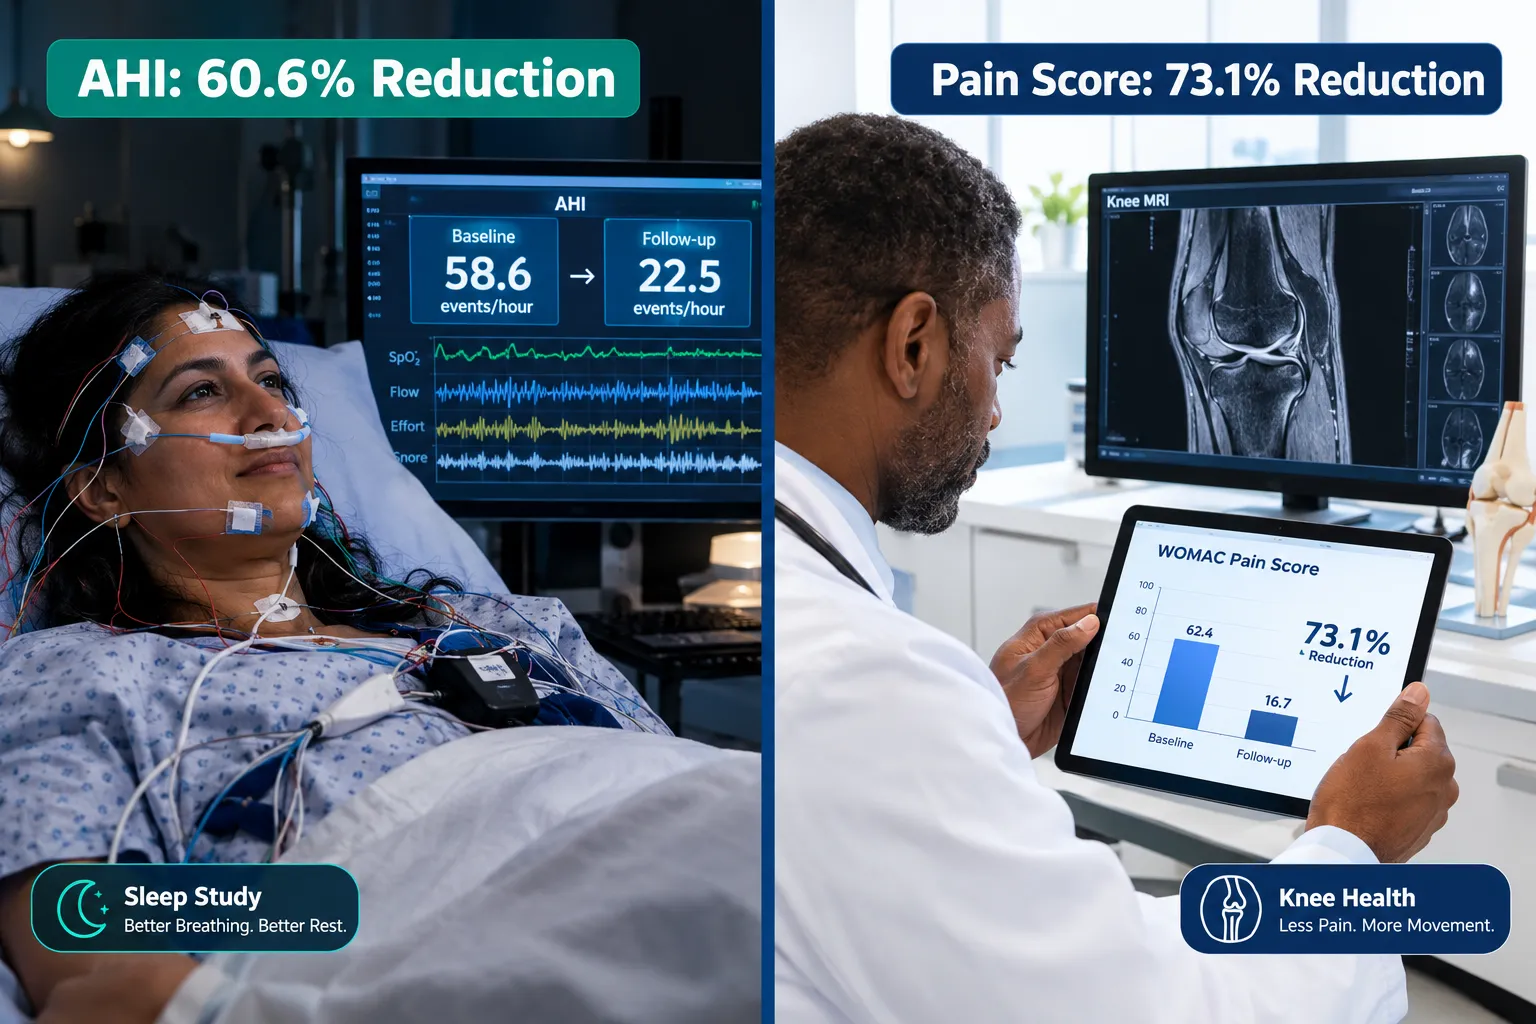
  • In knee OA, retatrutide reduced WOMAC pain scores by 73.1%; in OSA, AHI fell by 60.6%, roughly 36 fewer breathing pauses per hour.
  • Co-primary endpoint designs (pairing a disease-specific measure with percent body weight change) are now a model strategy for obesity-linked comorbidities.
  • Full peer-reviewed publications are still pending; most detailed data currently come from company releases and congress presentations.

Why Endpoint Choice Defines What a Trial Can Prove

Clinical trials answer only the questions their endpoints ask. In obesity research, percent change in body weight is a well-validated primary measure, but it cannot tell a regulator whether a patient's knee hurts less or whether their airway stays open at night. That gap is exactly why the retatrutide Phase 3 results for sleep apnea and osteoarthritis demand a closer look at endpoint selection methodology.

The TRIUMPH program enrolled 2,339 adults in its flagship obesity trial (TRIUMPH-1), with predefined subsets for knee OA and OSA. Mean weight loss reached 25.9% at the 9 mg dose and 28.3% at 12 mg over 80 weeks. Those figures are powerful, but they served as the platform from which disease-specific endpoints could be evaluated, not as a substitute for them.

Why Endpoint Choice Defines What a Trial Can Prove

Researchers working with GLP-3 Reta peptide materials in preclinical settings face a comparable decision: a biomarker of metabolic activity alone will not capture tissue-level or airway-level outcomes without a purpose-built measurement tool.


Retatrutide Phase 3 Results for Sleep Apnea: The AHI as a Precision Tool

The AHI counts how many times per hour breathing stops or becomes dangerously shallow during sleep. It is the gold-standard disease-specific endpoint for OSA trials because it directly quantifies the pathology, not just a correlate of it.

In participants with moderate-to-severe OSA and obesity, retatrutide reduced AHI by approximately 36.1 events per hour, a 60.6% drop from a baseline of 58.6 events per hour. Clinical commentary from 2026 notes that this reduction appears larger than what weight loss alone would predict, suggesting the AHI was sensitive enough to detect both respiratory and weight-mediated mechanisms simultaneously.

Why AHI worked here:

  • It is continuous, allowing detection of graded improvement.
  • It has established regulatory precedent as a primary endpoint in sleep apnea device and drug trials.
  • It separates responders from non-responders in a way that subjective sleepiness scores cannot.

Secondary measures that strengthen AHI data:

Endpoint Category Example Measure What It Adds
Subjective sleep quality Epworth Sleepiness Scale Patient-reported burden
Cardiometabolic safety Blood pressure, HbA1c Systemic risk context
Body composition Percent fat mass Weight-mediated pathway
Daytime function Patient global impression Functional relevance

Retatrutide Phase 3 Results for Sleep Apnea: The AHI as a Precision Tool

Researchers evaluating retatrutide through the GLP1-Reta research overview will recognize that the triple agonist mechanism, targeting GIP, GLP-1, and glucagon receptors, creates multiple physiological pathways, each of which may need its own measurement instrument.


Retatrutide Phase 3 Results for Osteoarthritis: Applying the WOMAC Subscale Correctly

Knee osteoarthritis endpoints present a different challenge: pain is subjective, functional limitation varies by patient, and structural changes on imaging may not correlate with symptoms in the short term. The TRIUMPH-4 trial addressed this by selecting the WOMAC pain subscale as one co-primary endpoint alongside percent body weight change.

Results showed a mean reduction of 4.3 points (73.1%) from a baseline WOMAC pain score of 6.0. That magnitude is clinically meaningful by any established threshold for minimal clinically important difference (MCID) in knee OA research.

What makes the WOMAC pain subscale the right choice:

  • Disease specificity: It targets pain in the knee joint, not global pain or mood.
  • Regulatory familiarity: Accepted by the FDA and EMA in prior OA drug approvals.
  • Sensitivity to change: Its five-item format detects graded improvement across activities.
  • Patient relevance: Items map directly to daily-life tasks like stair climbing and walking.

The co-primary design, requiring both the WOMAC pain subscale and percent body weight change to meet significance, is particularly important. It forces the trial to demonstrate that symptom relief is not simply a product of patients moving more because they weigh less. It separates the mechanical unloading benefit from any direct anti-inflammatory or analgesic effect.

Researchers interested in complementary tissue-level mechanisms can review related work on SS-31 mitochondrial research themes and SS-31 10mg research peptide considerations as examples of how endpoint granularity differs across biological pathways.


Building a Dual-Endpoint Strategy: A Practical Framework for Researchers

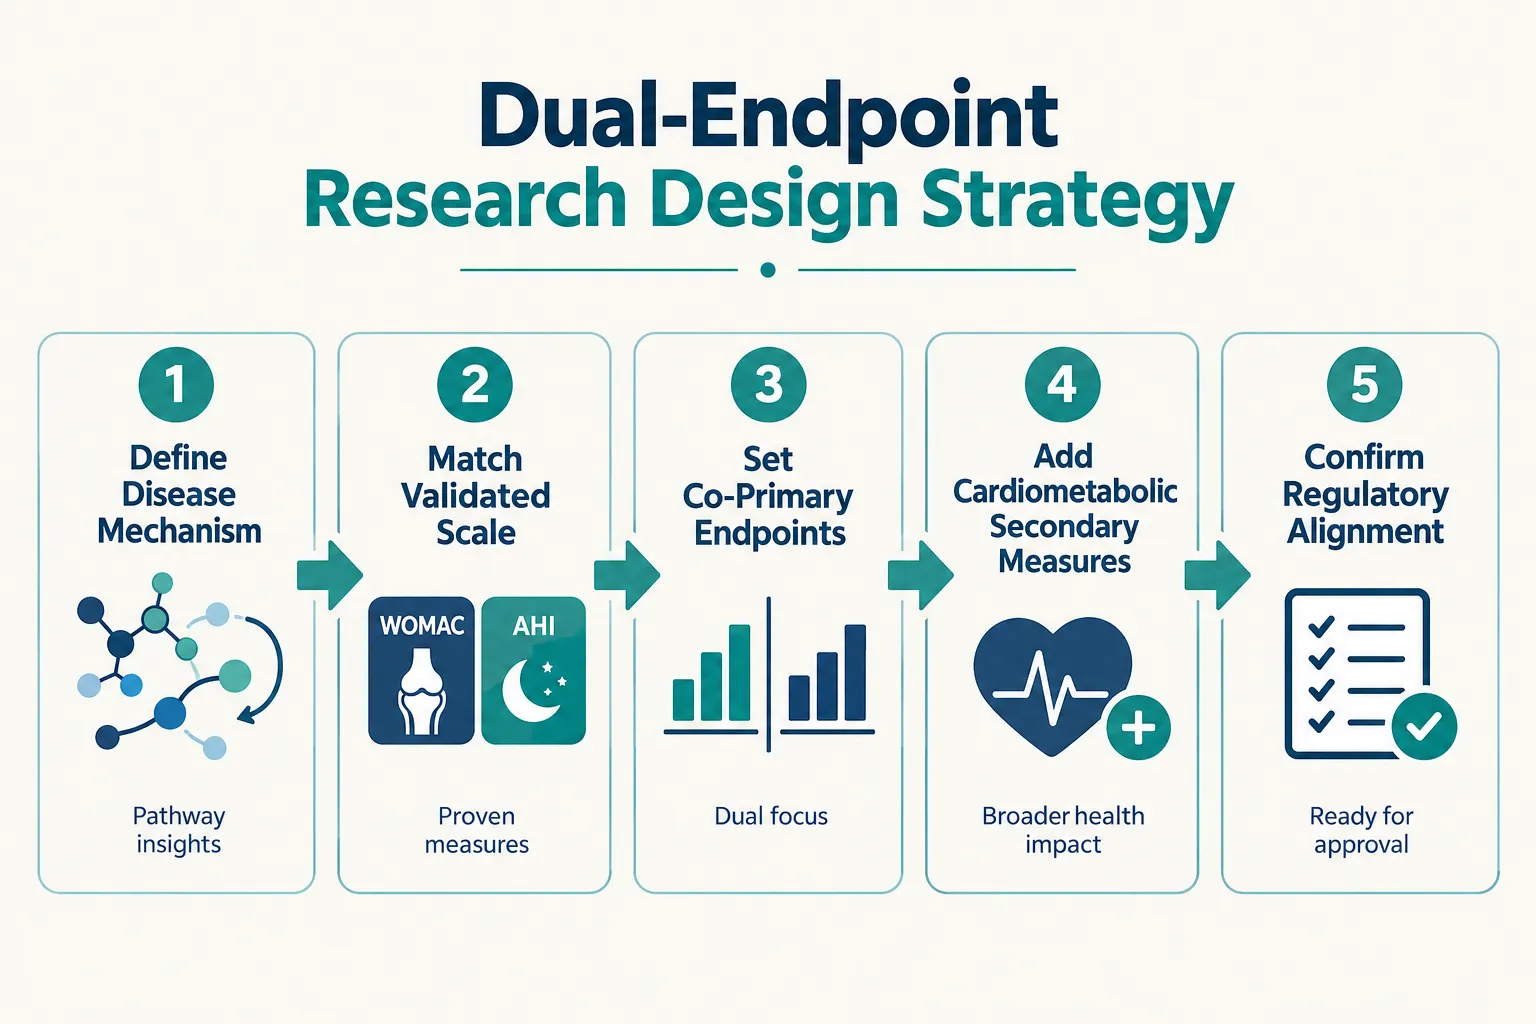
The TRIUMPH program's most transferable contribution may be its endpoint architecture. Across all four trials, Lilly paired a disease-specific primary measure with percent body weight change, then added cardiometabolic and functional secondary endpoints.

Building a Dual-Endpoint Strategy: A Practical Framework for Researchers

Researchers designing their own studies can apply this logic in five steps:

  1. Identify the dominant disease mechanism, airway collapse, joint degradation, glycemic dysregulation, or another target.
  2. Select a validated, regulatory-precedented instrument, AHI for OSA, WOMAC for OA, HbA1c for diabetes.
  3. Pair it with a weight-change measure when obesity is a contributing factor, creating a co-primary structure.
  4. Add functional and patient-reported secondary outcomes to capture daily-life impact.
  5. Include cardiometabolic safety endpoints to satisfy regulatory risk-benefit expectations.

This framework is relevant not only for large Phase 3 programs but for any investigator planning endpoint-driven preclinical or early-phase research. Resources on how to buy Reta and where to buy Reta for research-grade supply are available for investigators setting up controlled studies.

A key principle drawn from the TRIUMPH data: if the chosen endpoint is not sensitive enough to detect the full mechanism of action, a genuinely effective intervention can appear weaker than it is. The 60.6% AHI reduction likely would have been invisible if the trial had used body weight alone as its primary measure.


Conclusion

The retatrutide Phase 3 results for sleep apnea and osteoarthritis: how researchers should select disease-specific endpoints is not an abstract methodological question, it has direct consequences for what regulators see, what clinicians can act on, and what patients ultimately receive. The TRIUMPH program demonstrates that a triple agonist targeting metabolic pathways can produce profound, measurable improvements in OSA and knee OA, but only because the trials were designed to look for those improvements with the right tools.

Actionable next steps for researchers:

  • Use AHI as the primary endpoint for any OSA-adjacent intervention study; pair it with at least one cardiometabolic secondary measure.
  • Apply the WOMAC pain subscale as a co-primary alongside body weight change when studying obesity-related joint disease.
  • Review the TRIUMPH co-primary design structure before finalizing any protocol that addresses an obesity comorbidity.
  • Monitor peer-reviewed publications from the TRIUMPH program as they become available, since full datasets will refine secondary endpoint interpretations.
  • Consult the Reta 30mg research tag and GLP-3 Reta 20mg product page for research-grade material specifications relevant to dose-ranging studies.

Disease-specific endpoints do not just measure outcomes, they define what a drug is allowed to become.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-results-for-sleep-apnea-and-osteoarthritis-how-researchers-s.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-21 13:05:412026-10-21 13:05:41Retatrutide Phase 3 Results for Sleep Apnea and Osteoarthritis: How Researchers Should Select Disease-Specific Endpoints
How to Interpret Weight Loss, A1C, and Discontinuation Rates in Retatrutide Research

How to Interpret Weight Loss, A1C, and Discontinuation Rates in Retatrutide Research

October 17, 2026/0 Comments/in Uncategorized/by

"

Professional () hero image with 'How to Interpret Weight Loss, A1C' in crisp white modern centered on a deep navy

A single phase-2 trial published in the New England Journal of Medicine reported mean body-weight reductions exceeding 17% at 24 weeks, a number that reshaped expectations for the entire incretin drug class. Yet that headline figure conceals at least six methodological layers that any serious researcher must unpack before drawing conclusions. Understanding how to interpret weight loss, A1C, and discontinuation rates in retatrutide research is not optional; it is the difference between actionable data and misleading benchmarks.

Key Takeaways

  • Percent weight loss and absolute weight loss tell different stories; always identify which metric a study reports.
  • A1C reductions must be read alongside baseline glycemic status, exposure duration, and dose level.
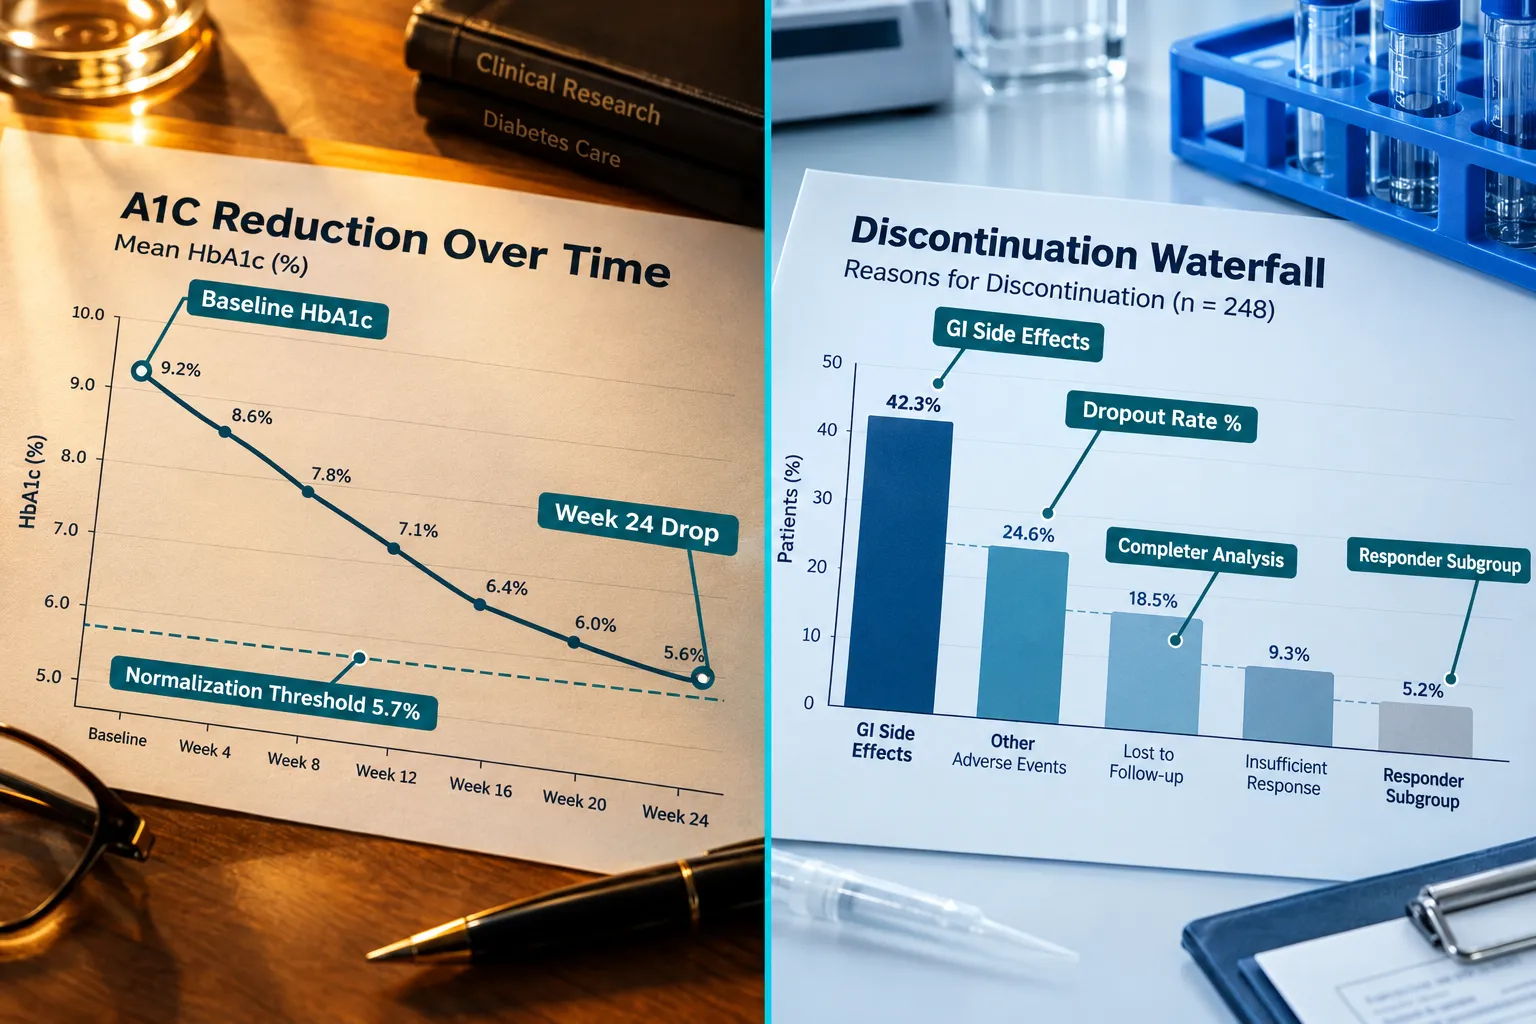
  • Discontinuation rates introduce survivorship bias; completer-only analyses inflate efficacy estimates.
  • Dose-escalation schedules vary across trials and directly affect both tolerability and endpoint timing.
  • Missing-data handling methods, such as last observation carried forward versus modified intent-to-treat, materially change how results should be interpreted.

Understanding the Metrics: A Research Checklist for Retatrutide Trials

Understanding the Metrics: A Research Checklist for Retatrutide Trials

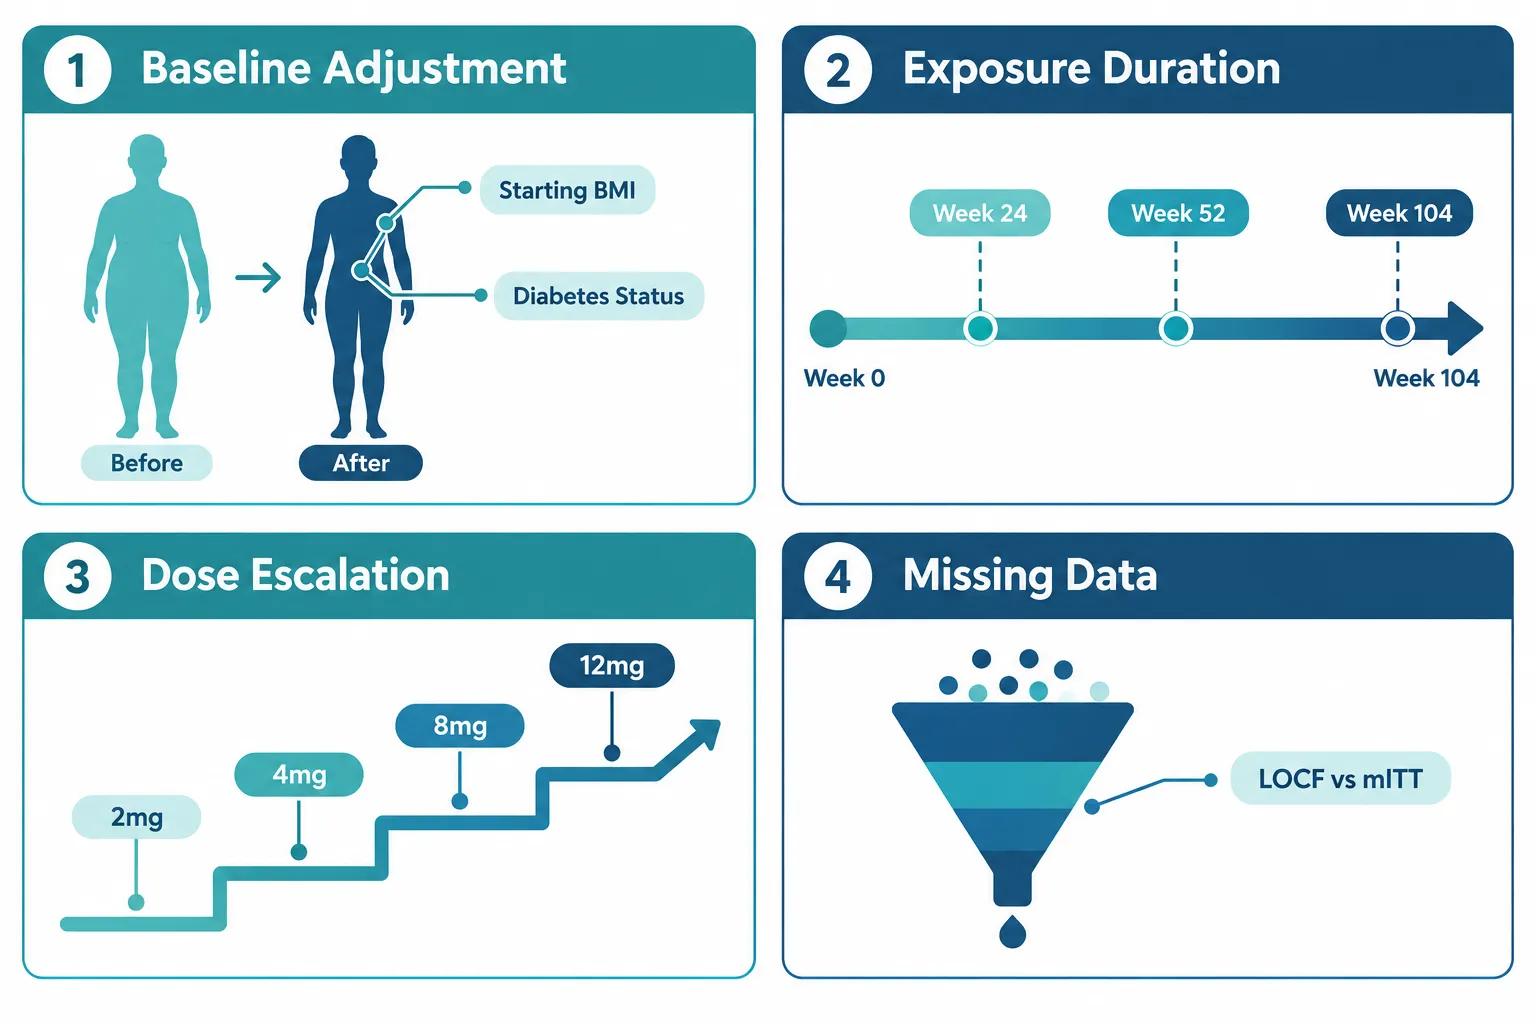
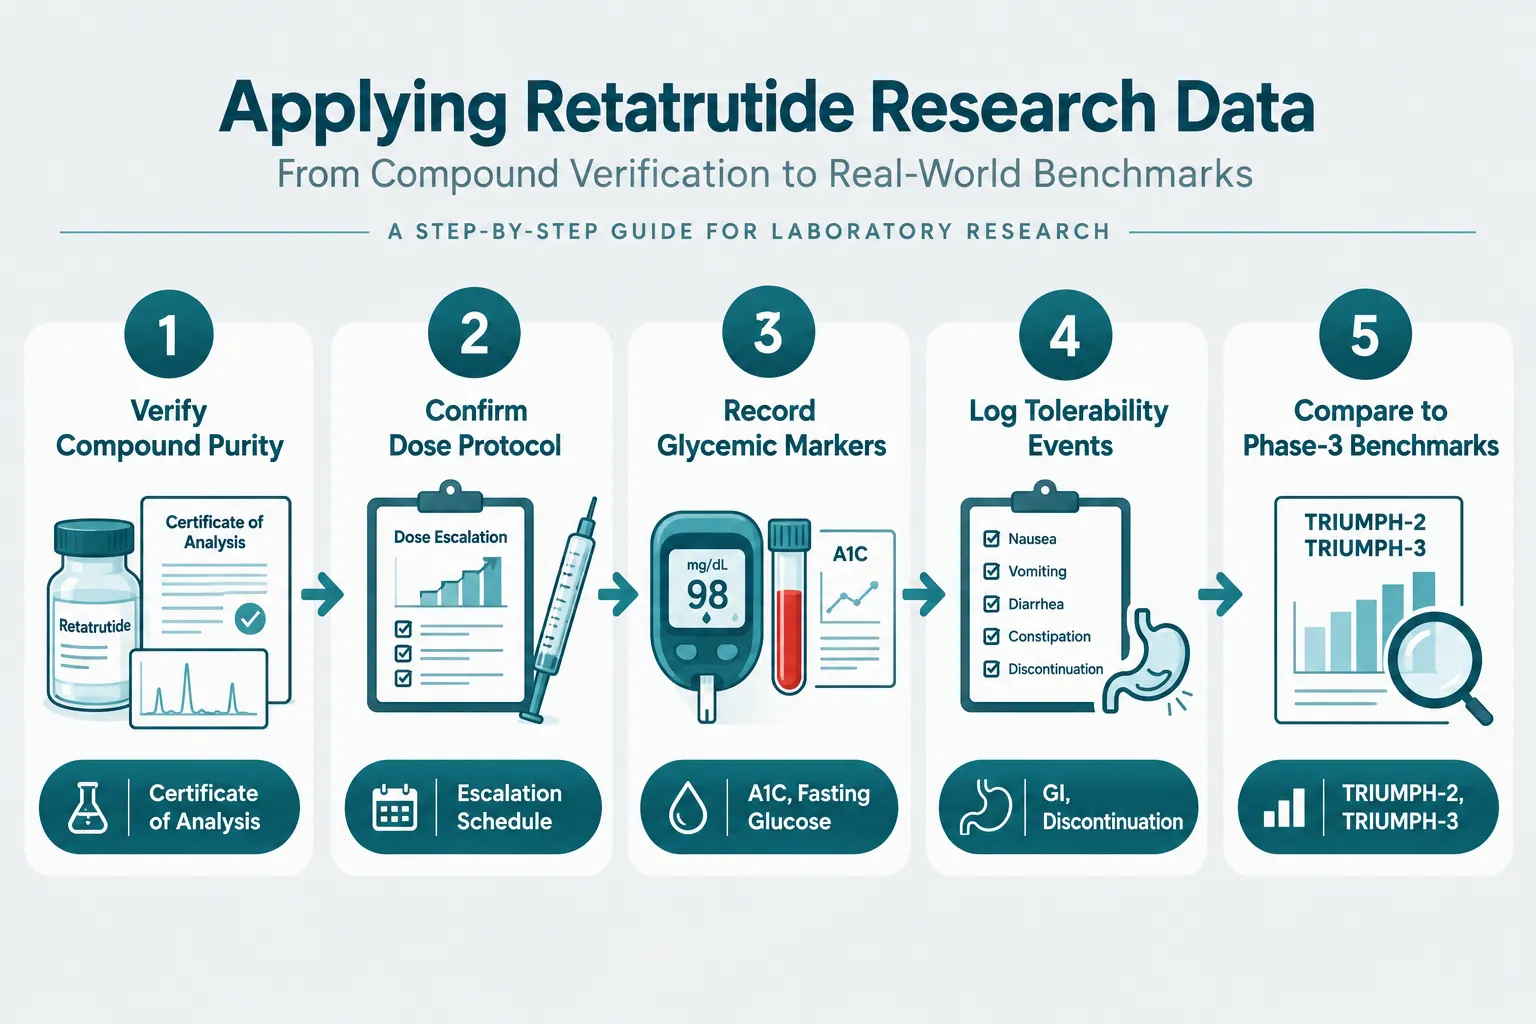
Before examining any specific endpoint, researchers reviewing retatrutide clinical trial data should build a structured checklist. Six variables consistently determine whether a reported number is comparable across studies.

1. Baseline adjustment. Weight-loss figures are meaningful only when the starting population is defined. TRIUMPH-3, the phase-3 obesity trial, enrolled adults with BMI of 30 or above without type 2 diabetes. TRIUMPH-2 enrolled adults with established type 2 diabetes, a population that typically shows attenuated weight loss due to disease-related metabolic differences. Comparing raw percentage figures between these two cohorts without baseline adjustment produces misleading conclusions.

2. Exposure duration. Long-term extension data from 2026 show approximately 30% mean weight loss at 104 weeks, roughly double the 24-week phase-2 figure. Researchers must anchor every efficacy claim to the exact week of assessment. A "24-week result" and a "2-year result" are not interchangeable data points.

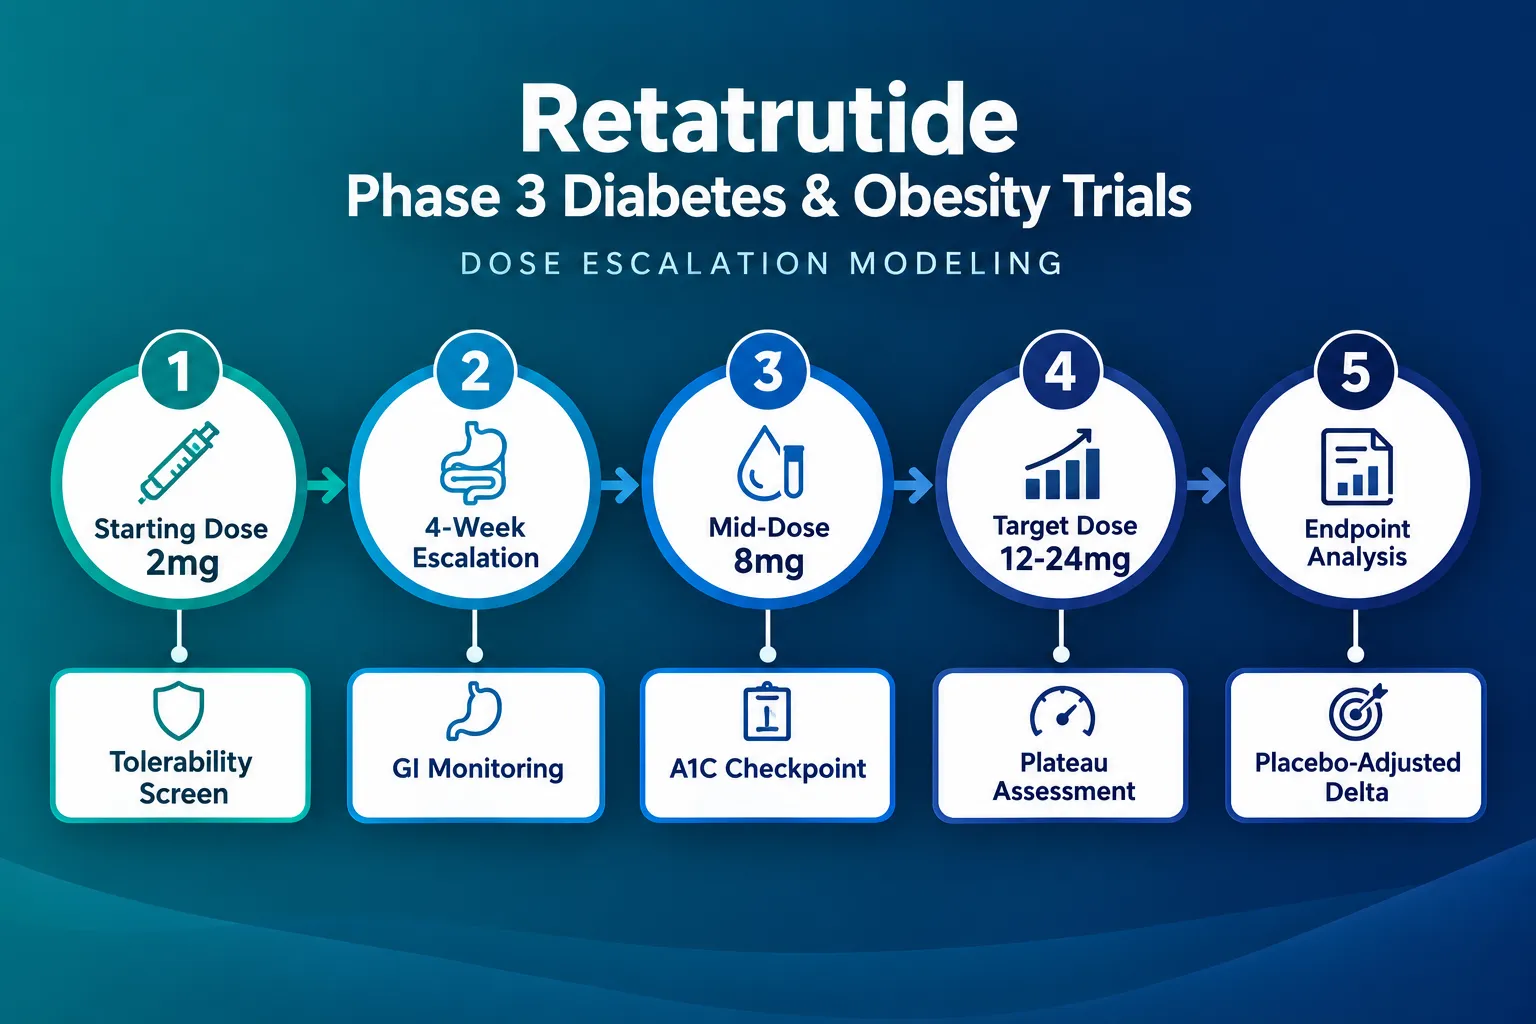
3. Dose-escalation protocol. Retatrutide is titrated upward through multiple dose levels (commonly 2 mg, 4 mg, 8 mg, and 12 mg). Studies that terminate at lower doses or that allow slower escalation will report lower efficacy and potentially different tolerability profiles. Always confirm which dose was active at the time of the reported endpoint.

4. Missing-data handling. The modified intent-to-treat (mITT) population includes all randomized participants who received at least one dose. Last observation carried forward (LOCF) substitutes the final recorded value for participants who dropped out. These two approaches can shift reported weight loss by several percentage points. TRIUMPH-3 used mITT analysis; researchers comparing it to earlier phase-2 data should verify that the same convention was applied.

5. Responder rates versus mean change. A mean weight loss of 24% can mask a bimodal distribution where a subset of participants lost 40% and another subset lost less than 10%. Responder analyses, reporting the proportion achieving at least 5%, 10%, or 15% body-weight reduction, provide a more complete picture for visceral fat research contexts.

6. Tolerability and its interaction with efficacy. Gastrointestinal adverse events are the primary driver of early discontinuation. Participants who tolerate the drug long enough to reach maximum dose will inevitably show better outcomes than the full randomized group. This creates a systematic upward bias in completer analyses.


How to Interpret A1C Data in Retatrutide Research

How to Interpret A1C Data in Retatrutide Research

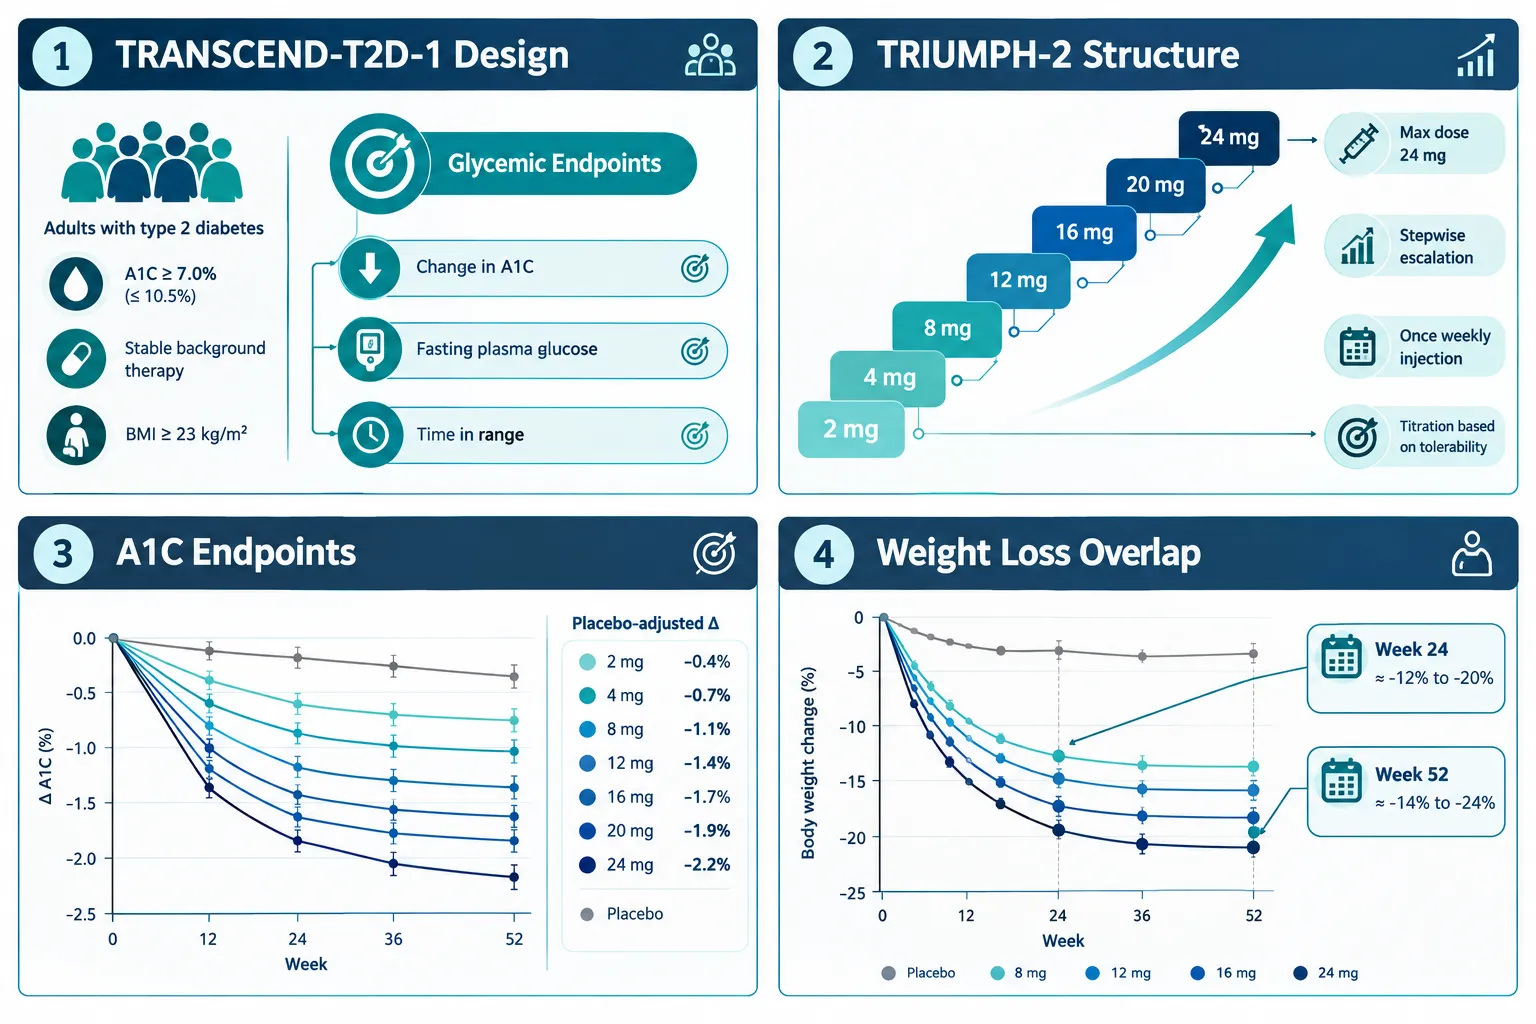
TRIUMPH-2 and the TRANSCEND-T2D-1 trial provide the most detailed glycemic data available as of 2026. TRANSCEND-T2D-1 reported A1C normalization, defined as reaching below 5.7%, in a substantial proportion of participants with type 2 diabetes, a result that positions retatrutide well above standard-of-care benchmarks. However, interpreting these numbers requires the same checklist discipline applied to weight-loss data.

"An A1C reduction from 8.5% to 6.2% and a reduction from 7.1% to 5.6% both represent meaningful clinical change, but they are not equivalent achievements and should never be averaged without stratification."

Baseline glycemic status matters most. A participant entering a trial with an A1C of 9% has more room to show a dramatic reduction than one starting at 7.2%. Meta-analytic reviews from 2025 and 2026 consistently flag this as the largest source of heterogeneity across retatrutide glycemic studies.

Concurrent weight loss confounds attribution. Because retatrutide acts on GLP-1, GIP, and glucagon receptors simultaneously, A1C improvements reflect both direct receptor-mediated effects and indirect benefits from weight reduction. Researchers should look for subgroup analyses that isolate glycemic response in participants with minimal weight loss to disentangle these mechanisms.

Dose level and A1C. Higher doses correlate with greater A1C reductions, but the dose-response curve flattens above 8 mg in most reported analyses. Citing an A1C result without specifying the active dose renders the figure nearly uninterpretable.

For researchers exploring related GLP-1 Reta receptor agonist mechanisms, understanding how triple-agonist activity differs from dual-agonist comparators is essential context for any glycemic endpoint.


Discontinuation Rates and What They Mean for Research Validity

Discontinuation Rates and What They Mean for Research Validity

TRIUMPH-3 reported discontinuation rates that, while lower than some earlier incretin trials, still warrant careful analysis. Approximately 10 to 16% of participants discontinued due to adverse events, primarily nausea, vomiting, and diarrhea, rates consistent with the class but not trivial.

Why discontinuation bias matters. When a trial reports efficacy only in completers, the remaining sample is systematically healthier and more tolerant. This is survivorship bias in its most direct form. A rigorous reading of how to interpret weight loss, A1C, and discontinuation rates in retatrutide research demands that readers identify whether the primary endpoint was calculated on the full mITT population or on completers only.

Sensitivity analyses are the gold standard. Well-designed trials include sensitivity analyses that model what outcomes would have looked like if all dropouts had remained on treatment. When sensitivity analyses produce results close to the primary analysis, confidence in the headline number increases substantially.

Safety signals from uncontrolled sources. Independent reporting in late 2026 highlighted safety concerns associated with counterfeit or improperly dosed buy Reta products circulating outside regulated research channels. These cases introduce noise into any real-world interpretation of tolerability data and underscore why sourcing integrity matters for laboratory use. Researchers seeking verified material should consult resources on where to buy Reta from tested, documented suppliers.

Regulatory implications. The FDA and other agencies evaluating retatrutide's approval pathway in 2026 have emphasized that labeling will reflect the full randomized population's outcomes, not completer subgroups. This distinction will directly affect how prescribing information frames expected weight loss and glycemic benefit in clinical practice.


Conclusion

Interpreting retatrutide research accurately requires more than reading the abstract. Researchers should apply a six-point checklist, baseline adjustment, exposure duration, dose escalation, missing-data method, responder rates, and discontinuation analysis, to every efficacy claim before drawing comparisons or designing follow-on studies.

Actionable next steps for researchers in 2026:

  • Obtain the full statistical analysis plan for any trial before interpreting its primary endpoint.
  • Cross-reference weight-loss figures against the specific week, dose level, and analysis population reported.
  • Treat completer-only A1C data as hypothesis-generating rather than confirmatory.
  • Verify that any retatrutide compound used in laboratory settings comes from a documented, purity-tested source to prevent contaminated data.
  • Review long-term extension data alongside short-term phase-2 benchmarks to contextualize trajectory, not just magnitude.

The science behind this triple-receptor agonist is advancing rapidly. Applying rigorous interpretive standards now ensures that research contributions to this field remain credible and reproducible.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/how-to-interpret-weight-loss-a1c-and-discontinuation-rates-in-retatrutide-resear.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-17 13:05:092026-10-17 13:05:09How to Interpret Weight Loss, A1C, and Discontinuation Rates in Retatrutide Research
Retatrutide Research vs Conventional Obesity Drugs: A Receptor- and Endpoint-Based Comparison

Retatrutide Research vs Conventional Obesity Drugs: A Receptor- and Endpoint-Based Comparison

October 10, 2026/0 Comments/in Uncategorized/by

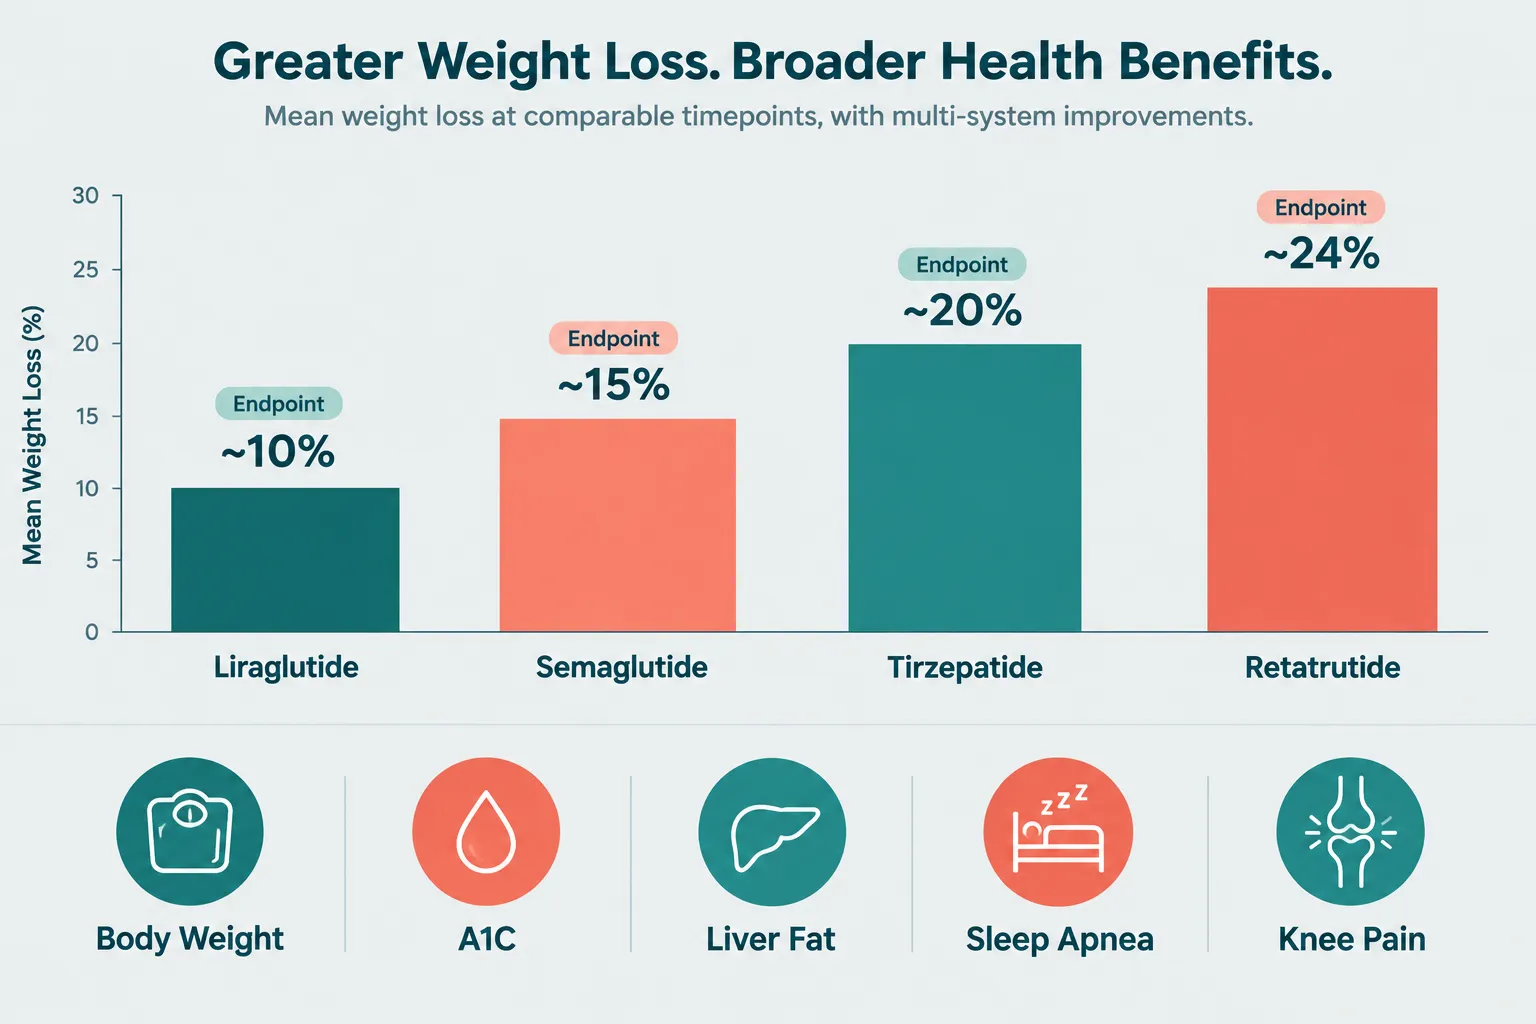
Obesity pharmacotherapy crossed a measurable threshold in 2026: a single investigational molecule achieved mean weight reductions of roughly 24 percent at 48 weeks in phase 2 trials, and up to 25 percent over 80 weeks in phase 3 data, numbers that no approved obesity drug had reached before. That molecule is retatrutide (LY3437943), and understanding why it performs differently from established agents requires a close look at receptor biology, not just headline weight numbers. This article provides a structured Retatrutide Research vs Conventional Obesity Drugs: A Receptor- and Endpoint-Based Comparison, examining how triple agonism changes the pharmacological landscape across food intake, energy expenditure, glycemic control, and tolerability endpoints.

Key Takeaways

  • Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, a mechanism that goes beyond the single or dual receptor targeting of all currently approved obesity drugs.
  • Phase 3 TRIUMPH-1 data show mean weight losses of up to 25 percent at 80 weeks, exceeding typical results for semaglutide and approaching or surpassing tirzepatide benchmarks.
  • Beyond weight, retatrutide trials measure endpoints including liver fat, sleep apnea indices, knee osteoarthritis pain, and A1C, reflecting a multi-system strategy.
  • A 2025 meta-analysis found no statistically significant difference in overall adverse event rates between retatrutide and comparator groups, suggesting the efficacy gains do not come with a proportional safety cost.
  • As of late 2026, retatrutide remains investigational; multiple phase 3 readouts have been reported, and a regulatory filing window is anticipated in late 2026 to 2027.

Receptor Biology: Where the Comparison Begins

Receptor Biology: Where the Comparison Begins

Every approved obesity drug in current clinical use targets at most two hormone receptors. Liraglutide and semaglutide are selective GLP-1 receptor agonists. Tirzepatide, the most recent approval, adds GIP receptor co-agonism. Retatrutide extends this architecture by adding full glucagon receptor activation, making it a triple hormone receptor agonist.

Each receptor contributes a distinct physiological role:

  • GLP-1 receptor activation slows gastric emptying, suppresses appetite through central and peripheral pathways, and stimulates glucose-dependent insulin release.
  • GIP receptor activation amplifies insulin secretion and may reduce nausea associated with GLP-1 agonism, partly explaining why dual agonists are often better tolerated at high doses than single GLP-1 agonists.
  • Glucagon receptor activation increases hepatic glucose output in a fasting state and, more importantly for obesity therapy, raises energy expenditure through thermogenic mechanisms.

This third receptor is the key differentiator. No approved obesity drug currently engages glucagon receptor signaling in a meaningful therapeutic way. By doing so, retatrutide addresses energy expenditure directly, a pathway that GLP-1-only drugs do not substantially activate. For a deeper look at how GLP-1 receptor biology intersects with retatrutide's design, see the GLP-1 Retatrutide overview and the dedicated Retatrutide Clinical Trials resource.

"Triple agonism is not simply an additive effect, it is a coordinated engagement of appetite, insulin sensitivity, and caloric burn that single-pathway drugs cannot replicate by design."


Efficacy Endpoints: Weight Loss, Glycemic Control, and Beyond

Efficacy Endpoints: Weight Loss, Glycemic Control, and Beyond

A rigorous Retatrutide Research vs Conventional Obesity Drugs: A Receptor- and Endpoint-Based Comparison must go beyond weight percentages and examine the full endpoint profile.

Weight Loss Benchmarks Across Drug Classes

The table below summarizes approximate mean weight reductions from pivotal trials across drug classes:

Agent Receptor Target Approx. Mean Weight Loss Trial Duration
Liraglutide GLP-1 ~8-10% 56 weeks
Semaglutide GLP-1 ~15% 68 weeks
Tirzepatide GIP + GLP-1 ~20-22% 72 weeks
Retatrutide GIP + GLP-1 + Glucagon ~23-25% 48-80 weeks

Phase 3 TRIUMPH-1 data in adults with obesity but without diabetes reported weight changes of -17.6 percent at 4 mg, -23.7 percent at 9 mg, and -25.0 percent at 12 mg, compared with -3.9 percent for placebo. These results represent a statistically and clinically meaningful separation from all approved comparators.

Glycemic Endpoints: TRIUMPH-2 and the Diabetes Population

TRIUMPH-2 evaluated retatrutide in adults with type 2 diabetes and obesity over 80 weeks. All three studied doses (4, 9, and 12 mg) delivered substantial body weight reduction alongside significant A1C reduction versus placebo. A 2025 meta-analysis confirmed mean A1C reductions of approximately 0.91 percent and fasting plasma glucose reductions of roughly 23.5 mg/dL across pooled retatrutide studies. This dual-endpoint performance is relevant when comparing retatrutide to GLP-1 agonists, which already improve both parameters but generally achieve smaller relative weight reductions at comparable timepoints.

Multi-System Endpoints: The Receptor-Driven Advantage

This is where the comparison becomes most striking. TRIUMPH-1 phase 3 data showed that retatrutide also reduced knee osteoarthritis pain scores and decreased apnea-hypopnea events in participants with obstructive sleep apnea. A phase 2a trial in metabolic dysfunction-associated steatotic liver disease (MASLD) demonstrated meaningful reductions in hepatic fat content and liver enzyme levels. A 2025 meta-analysis also documented systolic blood pressure reductions of approximately 9.9 mm Hg.

Earlier GLP-1-only programs rarely incorporated these endpoints within a single trial design. The breadth of retatrutide's endpoint coverage, spanning liver fat, sleep architecture, joint pain, glycemic control, and cardiovascular risk markers, reflects a receptor-driven strategy that treats obesity as a systemic disease rather than a weight number. For related research on combined peptide approaches, the Cagrilintide and Retatrutide comparison offers additional context. Readers interested in how noradrenergic mechanisms compare to incretin-based pathways may also find the Tesofensine mechanism vs incretin-based GLP-1 pathways analysis useful.


Tolerability, Dosing, and the Phase 3 Program

Tolerability, Dosing, and the Phase 3 Program

A complete Retatrutide Research vs Conventional Obesity Drugs: A Receptor- and Endpoint-Based Comparison must address safety alongside efficacy.

Gastrointestinal Tolerability

Like all GLP-1-based drugs, retatrutide produces gastrointestinal adverse events, primarily nausea, vomiting, and diarrhea. However, the 2025 meta-analysis found no statistically significant difference in overall adverse event rates between retatrutide and comparator groups (relative risk 1.11, p=0.24). This finding is notable: the additional glucagon receptor engagement does not appear to substantially increase the total adverse event burden compared with single or dual agonists.

Lilly has designed a dedicated phase 3 trial specifically to evaluate different dose-escalation regimens over approximately 113 weeks and 26 visits, directly addressing the practical challenge of tolerability at higher doses.

Once-Weekly Dosing and the Broader TRIUMPH Program

Retatrutide is administered as a once-weekly subcutaneous injection at doses ranging from 1 mg to 12 mg, with gradual titration. This matches the dosing frequency of semaglutide and tirzepatide, which simplifies head-to-head comparisons and supports potential clinical adoption.

The TRIUMPH phase 3 program extends across at least seven additional trials covering:

  • TRIUMPH-3: Severe obesity (BMI 35+) with established cardiovascular disease
  • TRIUMPH-4: Knee osteoarthritis
  • Moderate-to-severe obstructive sleep apnea
  • Chronic low back pain
  • MASLD / steatotic liver disease
  • Cardiorenal outcomes

Most of these trials are expected to complete in 2026, with a potential regulatory filing anticipated in late 2026 or 2027 if safety data remain consistent. As of late 2026, retatrutide remains investigational with no approved indication. Research-grade formulations referenced in resources such as GLP-3 Reta Cag 10mg and Reta 20mg are available for preclinical and laboratory research contexts only.


Conclusion

The receptor-and-endpoint lens makes the comparison clear. Conventional GLP-1 agonists work primarily through appetite suppression and slowed gastric emptying. Dual GIP/GLP-1 agonists add insulin sensitization and improved tolerability at higher doses. Retatrutide's triple agonism introduces glucagon receptor-driven energy expenditure as a third mechanism, and the clinical data show this translates into measurably greater weight loss and a broader multi-system endpoint profile than any currently approved agent.

Actionable next steps for researchers and clinicians:

  1. Review the full TRIUMPH phase 3 dataset as readouts continue through late 2026, paying particular attention to cardiovascular and MASLD endpoints.
  2. Compare tolerability profiles at equivalent dose-escalation schedules, not just peak doses, when evaluating retatrutide against tirzepatide or semaglutide.
  3. Monitor regulatory communications from Lilly for a potential New Drug Application filing window, currently anticipated in late 2026 to 2027.
  4. For preclinical research contexts, consult current literature on glucagon receptor co-agonism to understand the mechanistic basis for energy expenditure findings before extrapolating to clinical populations.

The data available in 2026 position retatrutide as the most efficacious pharmacological weight-loss agent studied to date, with a multi-system endpoint strategy that reframes obesity treatment as metabolic disease management rather than weight management alone.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-research-vs-conventional-obesity-drugs-a-receptor-and-endpoint-based.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-10 13:07:232026-10-10 13:07:23Retatrutide Research vs Conventional Obesity Drugs: A Receptor- and Endpoint-Based Comparison
Retatrutide Research Alternatives: Comparing Incretin Peptides, Tesofensine, and Metabolic Small Molecules by Endpoint Fit

Retatrutide Research Alternatives: Comparing Incretin Peptides, Tesofensine, and Metabolic Small Molecules by Endpoint Fit

October 9, 2026/0 Comments/in Uncategorized/by

Selecting the wrong compound for a metabolic research model does not just waste resources, it produces uninterpretable data. That problem is the core reason why retatrutide research alternatives: comparing incretin peptides, tesofensine, and metabolic small molecules by endpoint fit has become one of the most practical questions in preclinical and translational obesity science as of 2026. With retatrutide's TRIUMPH phase 3 program delivering landmark results, including a 23.7% mean body-weight reduction at 68 weeks in the TRIUMPH-4 trial, researchers now need a rigorous framework for matching comparator compounds to specific endpoint targets, not to marketing claims.

Key Takeaways

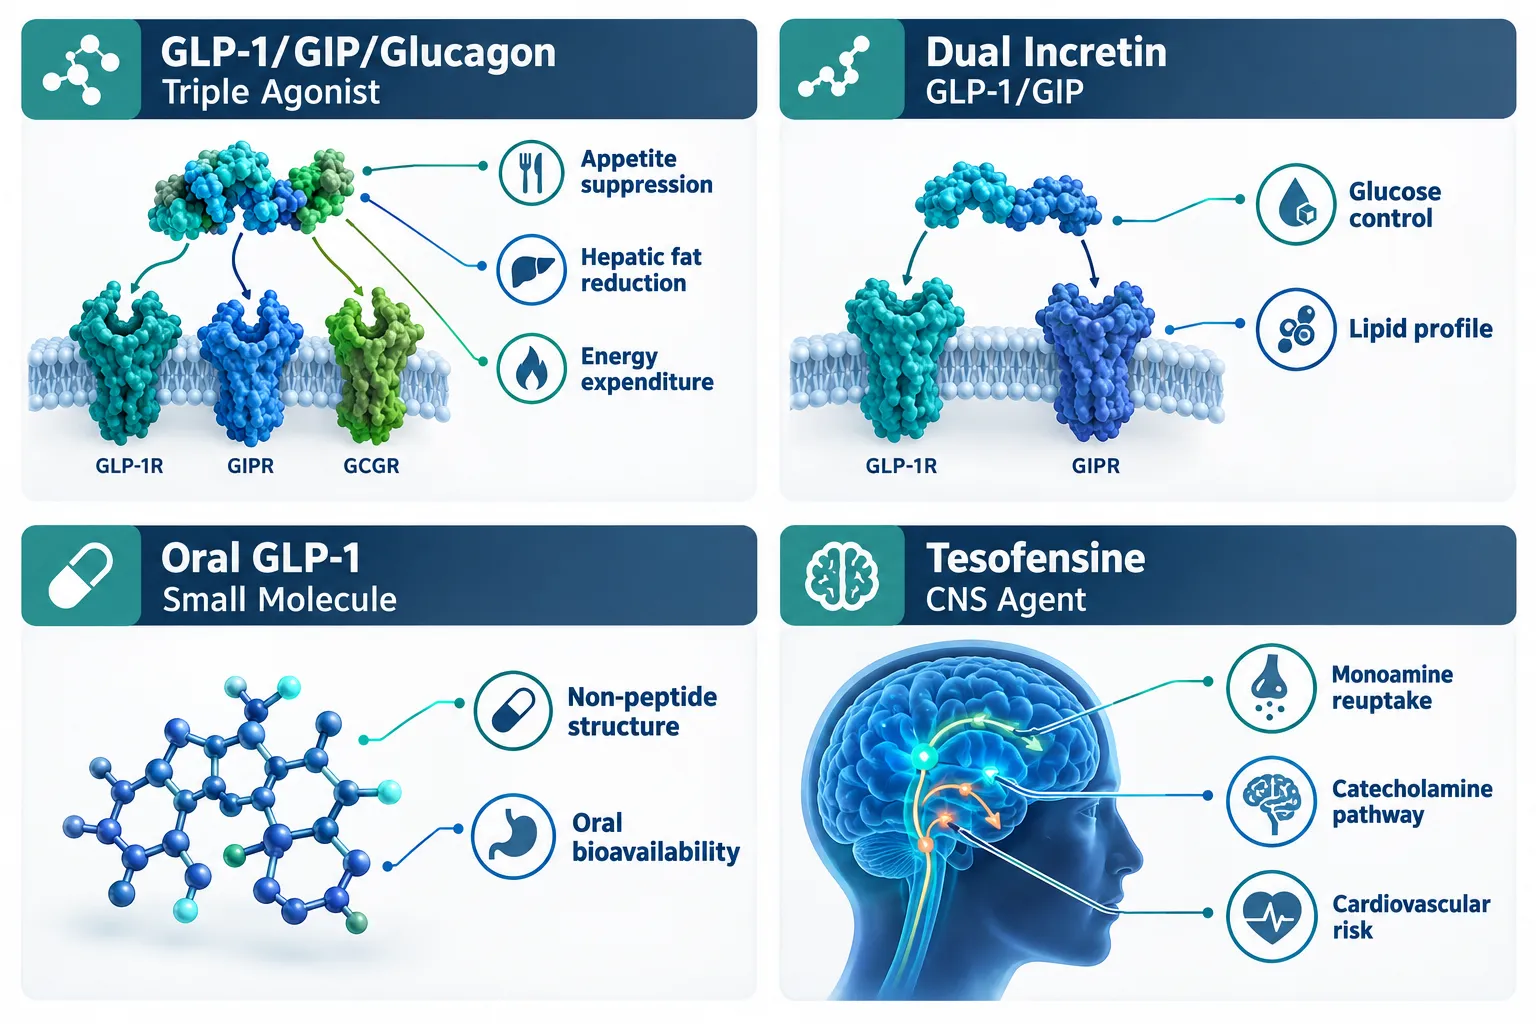
  • Retatrutide's triple agonist mechanism (GLP-1, GIP, glucagon receptors) produces the broadest endpoint coverage of any current incretin peptide, making it a high-bar comparator.
  • Dual incretin peptides like tirzepatide suit glucose and lipid endpoints but offer narrower energy-expenditure signaling than triple agonists.
  • Oral GLP-1 small molecules such as orforglipron expand access research but carry less mature phase 3 data than injectable incretin peptides.
  • Tesofensine addresses catecholamine and central appetite pathways but carries cardiovascular safety concerns that limit endpoint compatibility.
  • Model selection should begin with the primary endpoint, appetite, glucose, lipid, energy expenditure, catecholamine, or receptor signaling, before choosing a compound.

Why Endpoint Fit Matters More Than Compound Popularity

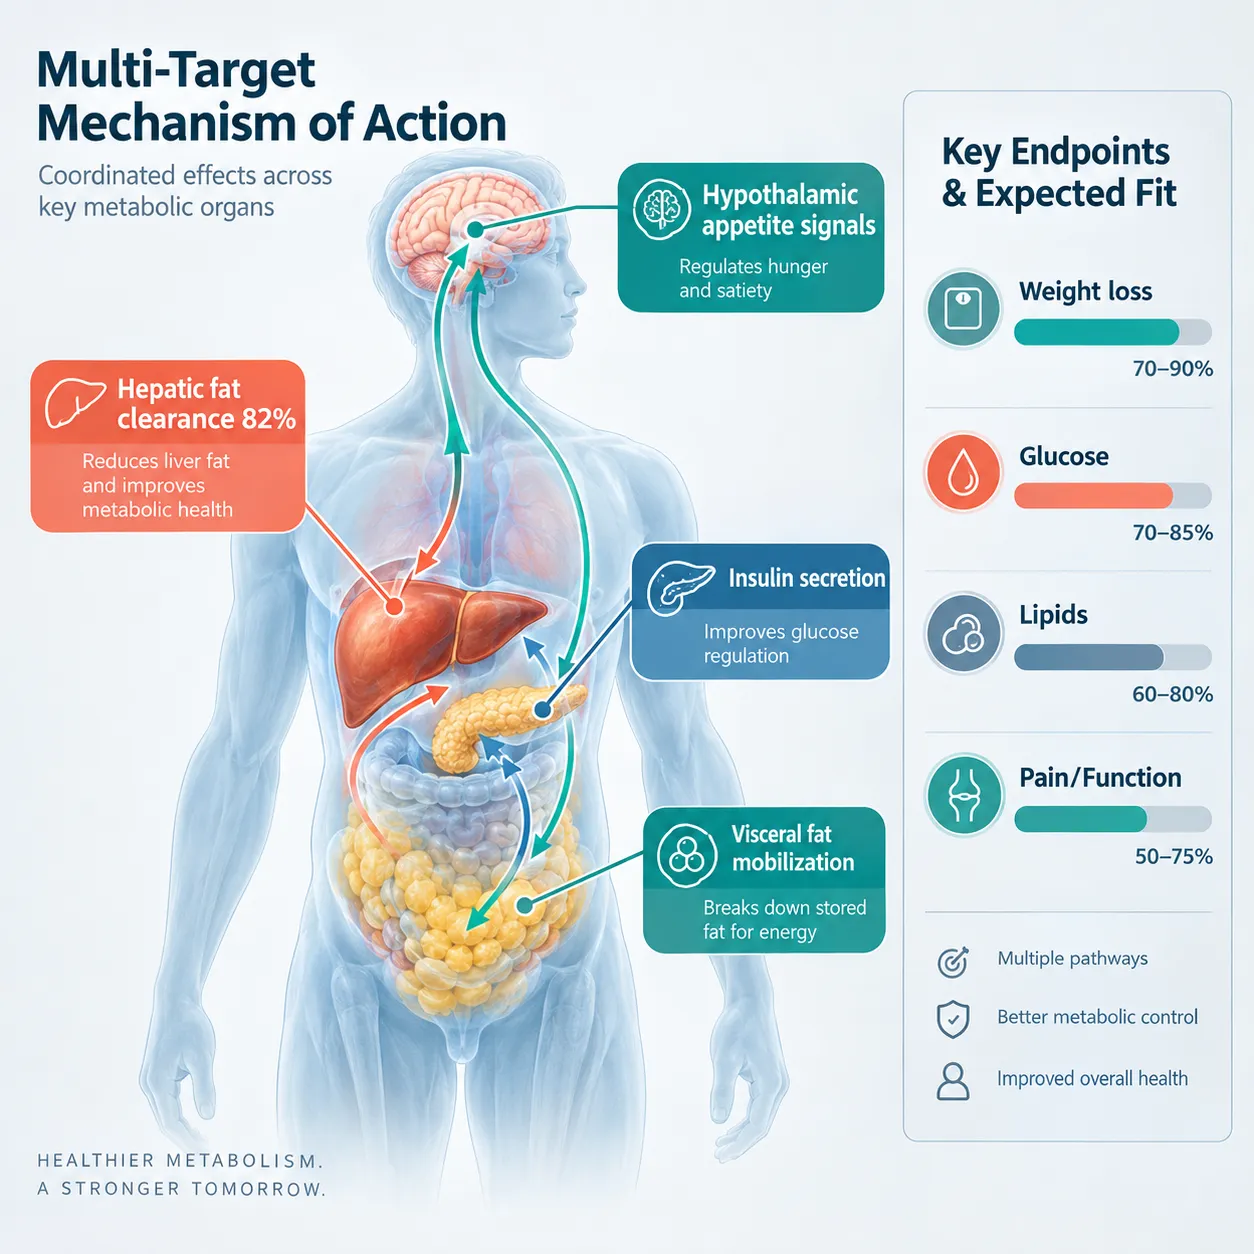
The metabolic research field in 2026 is crowded with potent compounds, and popularity is a poor proxy for scientific fit. Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, generating overlapping signals across appetite suppression, hepatic fat clearance, insulin secretion, and thermogenesis. Phase 2 data showed approximately 82% relative reduction in liver fat alongside a 24.2% mean weight loss at 48 weeks with the 12 mg dose. That breadth is valuable, but it also means retatrutide is a noisy tool when a study only needs to isolate one pathway.

Why Endpoint Fit Matters More Than Compound Popularity

A decision matrix built around the primary research endpoint cuts through this complexity. The six endpoint categories most relevant to metabolic compound selection are:

  • Appetite / satiety signaling, hypothalamic and vagal pathways
  • Glucose homeostasis, insulin secretion, HbA1c, fasting plasma glucose
  • Lipid metabolism, hepatic fat, triglycerides, LDL/HDL profiles
  • Energy expenditure, thermogenesis, resting metabolic rate, glucagon-driven brown adipose activation
  • Catecholamine / monoamine signaling, dopamine, norepinephrine, serotonin reuptake
  • Receptor-level signaling fidelity, clean agonism at a single receptor vs. multi-receptor crosstalk

Mapping each compound to these categories before designing a protocol prevents the most common error in metabolic research: choosing a compound because it produces the largest weight-loss number rather than because it isolates the pathway under investigation.


Incretin Peptides: Where Retatrutide and Its Closest Alternatives Sit

Among injectable incretin peptides, the comparison landscape in 2026 centers on three tiers of receptor engagement.

Retatrutide (GLP-1 / GIP / Glucagon triple agonist) is the highest-coverage option. The meta-analytic evidence across three randomized controlled trials confirms mean weight reduction of approximately 14.33%, BMI reduction of 5.38 units, and meaningful improvements in fasting plasma glucose, HbA1c, and blood pressure, all at very low statistical significance thresholds. For researchers studying retatrutide endpoints that span weight, metabolic, and musculoskeletal outcomes simultaneously, this breadth is the primary advantage. The TRIUMPH program's pairing of weight loss with pain endpoints in TRIUMPH-4 (knee osteoarthritis) and TRIUMPH-7 (chronic low back pain) illustrates this endpoint-fit strategy explicitly.

Tirzepatide (GLP-1 / GIP dual agonist) is the closest comparator for glucose and lipid endpoints without glucagon-driven thermogenesis. TRIUMPH-5 will provide direct head-to-head data against retatrutide in obesity, which will clarify how much the glucagon arm contributes to incremental weight loss and energy expenditure. Until those data arrive, tirzepatide remains the preferred compound when glucagon receptor crosstalk would confound interpretation.

Single GLP-1 receptor agonists (semaglutide class) offer the cleanest receptor-signaling fidelity for studies where isolating GLP-1R biology is the goal. For a broader overview of how these peptide classes are structured mechanistically, the Peptides 101 for Research-Use Only Buyers resource provides a useful structural and mechanistic foundation.

Researchers sourcing GLP-3/retatrutide analogs for preclinical work can review GLP-3 peptides for research use or explore lab tested peptides verified by third-party analysis to ensure compound integrity before endpoint data collection begins.


Tesofensine and Oral Small Molecules: Endpoint Fit for Catecholamine and Access Research

Tesofensine and Oral Small Molecules: Endpoint Fit for Catecholamine and Access Research

Tesofensine: A Legacy CNS Tool With a Narrow Endpoint Window

Tesofensine is a centrally acting triple monoamine reuptake inhibitor, blocking dopamine, norepinephrine, and serotonin reuptake, originally developed for neurodegenerative conditions. In mid-2000s obesity trials, it produced roughly 10-12% weight loss over approximately 24 weeks. That figure is meaningful in absolute terms but is substantially below the 20-24% range seen with retatrutide at higher doses.

More importantly, tesofensine's endpoint fit is narrow and specific:

Endpoint Category Tesofensine Fit Retatrutide Fit
Appetite / CNS satiety Strong (catecholamine) Strong (incretin)
Glucose homeostasis Weak Strong
Hepatic lipid reduction Weak Strong (~82% relative)
Energy expenditure Moderate (sympathomimetic) Strong (glucagon arm)
Cardiovascular safety margin Narrow (HR/BP elevation) Broader (phase 3 data)
Musculoskeletal pain endpoints Not established Active (TRIUMPH-4, 7)

Tesofensine is a legitimate research tool when the study question specifically involves catecholamine-mediated appetite suppression or monoamine pathway modulation. It is not a frontline alternative for glucose, lipid, or energy-expenditure endpoints, and its cardiovascular signal, increased heart rate and blood pressure, introduces confounders in cardiometabolic models. As of 2026, no new phase 3 obesity program for tesofensine has been widely reported, confirming its position as a legacy pharmacologic comparator rather than a contemporary competitor.

Oral GLP-1 Small Molecules: Orforglipron and the Access Endpoint

Orforglipron represents a structurally distinct category: a non-peptide, oral GLP-1 receptor agonist evaluated in the ATTAIN-1 trial for obesity. Its primary research value is not maximum weight-loss magnitude but oral bioavailability and adherence modeling. For studies where the endpoint involves treatment access, patient adherence behavior, or oral-route pharmacokinetics, orforglipron and related oral GLP-1 receptor agonists are the appropriate comparators.

The tradeoff is data maturity. As of early 2026, oral GLP-1 small molecules carry less complete phase 3 obesity data than injectable incretin peptides. Researchers designing studies that will need to reference a robust efficacy benchmark should note this gap when selecting comparators.


Building the Decision Matrix: Matching Compound to Research Question

The practical output of this analysis is a compound-selection protocol driven by the primary endpoint, not by compound prestige. The framework below summarizes the match:

Use retatrutide or a GLP-3 analog when:

  • The primary endpoint spans weight, metabolic markers, and functional outcomes simultaneously
  • Visceral fat research is a core outcome
  • Energy expenditure and glucagon-receptor biology are within scope

Use a dual incretin (tirzepatide class) when:

  • Glucose and lipid endpoints are primary, and glucagon-arm crosstalk would confound
  • Head-to-head incretin comparison is the study design

Use a single GLP-1 agonist when:

  • Receptor-signaling fidelity at GLP-1R alone is required
  • The study needs the cleanest possible GLP-1 pathway attribution

Use tesofensine when:

  • The research question is explicitly about monoamine reuptake inhibition or catecholamine-mediated satiety
  • Cardiovascular confounders are controlled for or are themselves the endpoint

Use oral GLP-1 small molecules when:

  • The endpoint involves oral-route pharmacology, adherence, or access modeling
  • Injectable peptide format is a study constraint

Building the Decision Matrix: Matching Compound to Research Question

Researchers reviewing the full retatrutide clinical trials landscape, including TRIUMPH-1 through TRIUMPH-8, will find that Eli Lilly's own endpoint-fit strategy mirrors this matrix: each TRIUMPH sub-study pairs retatrutide's weight-loss mechanism with a distinct comorbidity endpoint, from knee osteoarthritis pain to chronic low back pain to long-term weight maintenance. That design logic is directly transferable to preclinical model selection.

For researchers sourcing compounds, the TESA IPA blend peptide page offers a relevant example of how multi-mechanism blends are positioned for specific research applications, reinforcing the endpoint-fit principle at the product level.


Conclusion

The most consequential decision in metabolic peptide research is not which compound produces the largest effect size, it is which compound isolates the pathway the study is actually designed to interrogate. Retatrutide research alternatives: comparing incretin peptides, tesofensine, and metabolic small molecules by endpoint fit is not an academic exercise; it is a protocol-design requirement.

Actionable next steps for research teams in 2026:

  1. Define the primary endpoint category first, appetite, glucose, lipid, energy expenditure, catecholamine, or receptor signaling, before shortlisting compounds.
  2. Use retatrutide or GLP-3 analogs for broad metabolic and functional endpoint studies; use single-receptor agonists when signaling fidelity is paramount.
  3. Reserve tesofensine for CNS monoamine pathway studies with appropriate cardiovascular controls.
  4. Monitor TRIUMPH phase 3 readouts through 2026 to update the efficacy benchmarks used in comparator selection.
  5. Verify compound purity through third-party testing before any endpoint data collection begins, using lab tested peptides from verified suppliers.

Endpoint fit, not headline weight-loss numbers, is the standard that produces reproducible, interpretable metabolic research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-research-alternatives-comparing-incretin-peptides-tesofensine-and-me.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-09 13:10:262026-10-09 13:10:26Retatrutide Research Alternatives: Comparing Incretin Peptides, Tesofensine, and Metabolic Small Molecules by Endpoint Fit
GLP-3 Retatrutide and Oral GLP-1 Concepts: How Researchers Should Compare Exposure, Gastric Emptying, and Bioavailability

GLP-3 Retatrutide and Oral GLP-1 Concepts: How Researchers Should Compare Exposure, Gastric Emptying, and Bioavailability

October 9, 2026/0 Comments/in Uncategorized/by

}

Professional () hero image with 'GLP-3 Retatrutide and Oral GLP-1 Concepts' in crisp white modern centered on a deep teal

Fewer than one percent of an oral GLP-1 molecule typically survives the journey from stomach to systemic circulation, a stark contrast to the near-complete absorption seen with subcutaneous peptides. That single pharmacokinetic fact reshapes every study design attempting to compare retatrutide with oral GLP-1 agents. Understanding GLP-3 Retatrutide and Oral GLP-1 Concepts: How Researchers Should Compare Exposure, Gastric Emptying, and Bioavailability is not merely a matter of route preference; it demands rigorous attention to exposure matching, assay selection, and formulation controls before any meaningful head-to-head conclusion can be drawn.

Key Takeaways

  • Retatrutide is a triple agonist (GLP-1, GIP, and glucagon receptors), giving it a fundamentally different receptor profile than single-target oral GLP-1 agents.
  • Subcutaneous retatrutide achieves near-complete bioavailability; oral GLP-1 formulations typically reach less than 1%, requiring careful dose-normalization in comparative studies.
  • Gastric emptying slows significantly with retatrutide, but the effect attenuates over time, a tolerance pattern researchers must account for in endpoint timing.
  • Exposure matching via AUC and Cmax normalization is the critical first step before comparing pharmacodynamic outcomes across routes.
  • Study designs must control for formulation variables (e.g., SNAC absorption enhancers in oral agents) that independently affect gastric physiology.

Retatrutide's Molecular Profile and Why Route Matters

Retatrutide is a long-acting peptide that simultaneously activates GLP-1, GIP (glucose-dependent insulinotropic polypeptide), and glucagon receptors. This triple-agonist architecture sets it apart from oral GLP-1 receptor agonists, which typically target only the GLP-1 pathway. Researchers exploring GLP-1 Retatrutide mechanisms should note that the glucagon receptor component drives additional hepatic glucose output modulation and energy expenditure, effects absent from most oral comparators.

Retatrutide's Molecular Profile and Why Route Matters

Administered subcutaneously, retatrutide displays a half-life of approximately six days, enabling once-weekly dosing and predictable steady-state accumulation. Its bioavailability via this route approaches 100%. Oral GLP-1 agents, by contrast, face sequential degradation barriers: gastric acid, peptidase activity in the intestinal lumen, and extensive hepatic first-pass metabolism. Even with absorption enhancers such as sodium N-[8-(2-hydroxybenzoyl)amino]caprylate (SNAC), systemic exposure remains a fraction of the administered dose.

This gap is not a minor technical detail. It fundamentally changes what "equivalent dose" means across routes, and it is the first problem any comparative study design must solve.


Comparing Exposure: AUC Matching and Normalization Strategies

When researchers set out to apply GLP-3 Retatrutide and Oral GLP-1 Concepts: How Researchers Should Compare Exposure, Gastric Emptying, and Bioavailability to actual protocols, exposure normalization is the non-negotiable starting point. The standard approach uses area under the concentration-time curve (AUC) and peak plasma concentration (Cmax) as anchors.

Parameter Subcutaneous Retatrutide Oral GLP-1 Agent
Bioavailability ~100% <1%
Half-life ~6 days 12-14 hours (semaglutide oral)
Dosing frequency Once weekly Once daily
Steady-state variability Low Moderate-to-high

Key normalization steps for researchers:

  • Calculate molar AUC at steady state for each agent under study conditions.
  • Adjust oral doses iteratively until systemic AUC overlaps with the injectable comparator.
  • Document intra-subject variability in oral absorption, which is substantially higher than subcutaneous routes.
  • Account for food-state dependency: oral GLP-1 absorption drops sharply when taken with meals, while subcutaneous absorption is largely food-independent.

For labs sourcing materials, detailed product specifications for GLP-3 peptide (10mg, 99% pure, third-party tested) provide purity benchmarks that affect in vitro exposure calculations.


Gastric Emptying: Endpoints, Timing, and Tolerance

Gastric emptying slowing is a shared pharmacodynamic effect across GLP-1 class agents, but the magnitude, onset, and durability differ considerably between retatrutide and oral formulations.

Gastric Emptying: Endpoints, Timing, and Tolerance

With retatrutide, gastric emptying slows markedly in early treatment weeks. Scintigraphic studies show significant retention of gastric contents at four hours post-meal during dose escalation. Critically, this effect attenuates with continued exposure, a tolerance pattern driven by receptor desensitization and adaptive autonomic responses. By weeks 12 to 16 of continuous dosing, gastric emptying rates partially recover toward baseline even as plasma drug concentrations remain at steady state.

With oral GLP-1 agents, the gastric emptying effect is present but often less pronounced at clinically achievable systemic exposures. The SNAC excipient itself may exert local gastric effects independent of GLP-1 receptor activation, complicating interpretation of gastric emptying endpoints in oral-agent studies.

"Researchers who measure gastric emptying only at peak effect risk attributing a transient pharmacodynamic response to a sustained mechanism, a design flaw that inflates apparent potency differences between routes."

For comparative studies, the recommended approach is serial gastric emptying assessment at weeks 2, 8, and 16, capturing both peak effect and tolerance development. Acetaminophen absorption tests offer a practical surrogate when scintigraphy is unavailable.


Study Design Guidance for Comparing Routes

Applying GLP-3 Retatrutide and Oral GLP-1 Concepts: How Researchers Should Compare Exposure, Gastric Emptying, and Bioavailability to a rigorous protocol requires several additional controls beyond exposure matching.

Study Design Guidance for Comparing Routes

Formulation controls: SNAC and similar permeation enhancers alter gastric pH and mucosal permeability. Studies must include SNAC-only control arms to isolate GLP-1 receptor-mediated gastric effects from excipient-mediated ones.

Receptor specificity controls: Because retatrutide activates glucagon receptors, which independently influence gastric motility and hepatic metabolism, researchers comparing it to GLP-1-only oral agents should include receptor-selective antagonist arms where feasible.

GI tolerability endpoints: Nausea and vomiting rates differ across routes partly because of absorption rate differences. Subcutaneous delivery produces a slower Cmax rise than an oral bolus, which may translate to better early tolerability. Capturing time-to-event GI data alongside exposure metrics strengthens mechanistic interpretation.

Beyond obesity endpoints: Emerging research on metabolic dysfunction-associated steatotic liver disease (MASLD) and cardiometabolic markers requires longer observation windows. Researchers sourcing materials for extended studies can review options including GLP-3 Reta 20mg and GLP-3 Reta 30mg formats to support multi-week preclinical protocols.

For foundational background on peptide mechanisms relevant to this class, the Peptides 101 for Research-Use Only Buyers resource covers structure and receptor interaction concepts that inform study design. Researchers also comparing oral versus injectable delivery formats more broadly may find the Slupp332 Oral Versus Injectable Research analysis a useful methodological reference.


Conclusion

The comparison between retatrutide and oral GLP-1 agents is only as valid as the study design supporting it. Researchers in 2026 who treat route of administration as a secondary variable, rather than a primary pharmacokinetic determinant, risk generating data that cannot be meaningfully interpreted or replicated.

Actionable next steps for research teams:

  1. Begin every comparative protocol with AUC-matched exposure normalization, not nominal dose equivalence.
  2. Use serial gastric emptying assessments (weeks 2, 8, and 16 minimum) to capture tolerance development.
  3. Include SNAC-only control arms in any oral GLP-1 study measuring gastric endpoints.
  4. Pre-specify receptor-specificity controls when comparing multi-agonist injectables to single-agonist oral agents.
  5. Source verified, high-purity research materials, such as those available through the Buy Retatrutide Peptide catalog, to ensure compound integrity does not introduce confounding variables.

Rigorous attention to these pharmacokinetic and pharmacodynamic fundamentals is what separates publishable comparative data from inconclusive noise.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/glp-3-retatrutide-and-oral-glp-1-concepts-how-researchers-should-compare-exposur.webp 1254 1254 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-09 13:07:312026-10-09 13:07:31GLP-3 Retatrutide and Oral GLP-1 Concepts: How Researchers Should Compare Exposure, Gastric Emptying, and Bioavailability
Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation

Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation

October 8, 2026/0 Comments/in Uncategorized/by

Only one drug in the current cardiometabolic pipeline simultaneously activates GLP-1, GIP, and glucagon receptors, and its Phase 3 data are now reshaping how researchers design glycemic studies. Retatrutide Phase 3 diabetes data, drawn from the TRANSCEND and TRIUMPH trial programs, offer an unusually rich dataset for modeling the relationship between A1C reduction, glucose area under the curve (AUC), body weight loss, and structured dose escalation. For researchers building preclinical or translational models, understanding how to separate direct glycemic effects from weight-mediated effects is now a central methodological challenge.

Key Takeaways

  • Retatrutide Phase 3 diabetes data from TRANSCEND-T2D and TRIUMPH-2 provide robust endpoints for A1C, fasting glucose, and body weight in type 2 diabetes populations.
  • Glucose AUC and A1C timing data allow researchers to model direct glycemic receptor effects independently of body-weight-mediated insulin sensitization.
  • Dose escalation protocols in Phase 3 trials (ranging from 2 mg to 24 mg weekly) are critical variables when designing exposure-response research models.
  • Placebo-adjusted analysis is essential for isolating the true pharmacodynamic signal in both glycemic and weight outcomes.
  • The dual burden of hyperglycemia and obesity in trial populations makes retatrutide a uniquely informative compound for integrated cardiometabolic research.

Understanding the Phase 3 Trial Architecture

The TRANSCEND-T2D program is the dedicated diabetes efficacy arm of retatrutide's Phase 3 development. TRANSCEND-T2D-1 enrolled adults with type 2 diabetes and suboptimal glycemic control, using A1C reduction as the primary endpoint alongside fasting plasma glucose and body weight. The trial design included a structured dose escalation schedule, beginning at 2 mg weekly and titrating upward over several weeks to target maintenance doses of 8 mg or 12 mg.

Understanding the Phase 3 Trial Architecture

What makes this data particularly valuable for research modeling is the granularity of glycemic endpoints. A1C was measured at multiple timepoints, and continuous glucose monitoring data in select cohorts provided glucose AUC profiles across fasting and postprandial windows. This allows researchers to distinguish early pharmacodynamic effects, driven by direct receptor activation, from later improvements that correlate more closely with cumulative weight loss.

The broader TRANSCEND-T2D program extends follow-up to 52 weeks and beyond, providing chronic exposure data that are essential for modeling long-term glucose normalization trajectories. Researchers exploring Retatrutide Endpoints will find the TRANSCEND dataset particularly useful for establishing dose-response relationships across glycemic variables.


Separating Glycemic Effects from Weight-Mediated Effects in Retatrutide Phase 3 Diabetes Data

This is the core methodological question that Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation must address. Retatrutide produces two partially overlapping but mechanistically distinct effects: direct incretin-mediated glycemic control and indirect glycemic improvement driven by fat mass reduction and restored insulin sensitivity.

Separating Glycemic Effects from Weight-Mediated Effects in Retatrutide Phase 3 Diabetes Data

Direct glycemic effects are detectable early, often within the first four weeks, before significant weight loss has accumulated. These include:

  • Reduced fasting plasma glucose via GLP-1 receptor-mediated insulin secretion
  • Suppressed glucagon secretion through glucagon receptor agonism at pharmacological doses
  • Improved postprandial glucose AUC through slowed gastric emptying

Weight-mediated glycemic effects emerge later and are characterized by:

  • Progressive improvement in insulin sensitivity correlated with fat mass reduction
  • Declining HOMA-IR scores tracking body weight trajectory
  • A1C reductions that continue after glucose-lowering receptor effects plateau

"Placebo-adjusted A1C delta at Week 12 versus Week 52 provides a practical window for separating these two mechanisms in research model design."

The TRIUMPH-2 trial, which enrolled participants with both obesity and type 2 diabetes, is especially informative here. TRIUMPH-2 reported substantial A1C reductions alongside body weight losses exceeding 20% from baseline at higher doses. By comparing A1C trajectories against weight-loss kinetics, researchers can use time-lagged regression models to quantify the independent glycemic contribution of the drug's receptor activity.

For researchers interested in related dual-mechanism compounds, the Cagrilintide And Retatrutide combination data offer a complementary framework for modeling additive glycemic and weight effects.


Dose Escalation as a Research Variable: Modeling Exposure-Response Relationships

Dose escalation design is not merely a safety protocol, it is a primary research variable in Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation. The Phase 3 programs used weekly subcutaneous dosing with escalation steps at defined intervals, creating a natural dose-exposure ladder that researchers can exploit for pharmacokinetic-pharmacodynamic (PK-PD) modeling.

Dose Escalation as a Research Variable: Modeling Exposure-Response Relationships

Key dose escalation parameters from Phase 3 data include:

Escalation Stage Weekly Dose Primary Research Signal
Initiation 2 mg Tolerability, early GLP-1 effect
Mid-escalation 4-8 mg A1C inflection, glucose AUC shift
Maintenance 12-24 mg Maximum weight loss, sustained A1C

Phase 3b studies without diabetes populations provide a useful comparator, allowing researchers to isolate the weight-loss contribution to glycemic improvement by modeling the delta between diabetic and non-diabetic cohorts at equivalent doses.

For researchers sourcing compounds for preclinical work, GLP-1 Retatrutide and GLP-3 Retatrutide Buy Online USA pages provide relevant product information. Those evaluating quantity options may also review Reta 20mg For Sale and GLP-3 Reta 30mg For Sale for research-grade availability.

The TRIUMPH-1 and TRIUMPH-4 trials, focused primarily on obesity without diabetes, extend the dose-response dataset by providing weight-loss curves at equivalent dose levels without the confounding variable of baseline hyperglycemia. This cross-trial comparison is a powerful tool for building research models that quantify the glycemic benefit attributable solely to weight reduction.


Conclusion

Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation represents one of the most data-rich opportunities in current cardiometabolic research. The TRANSCEND and TRIUMPH programs together provide a structured, multi-dose, multi-timepoint dataset that enables researchers to disentangle direct receptor-mediated glycemic effects from weight-loss-driven improvements.

Actionable next steps for researchers:

  1. Use early-timepoint A1C and glucose AUC data (Weeks 4-12) to establish direct glycemic receptor effect baselines before significant weight loss accumulates.
  2. Apply placebo-adjusted analysis at each dose level to isolate the true pharmacodynamic signal from regression to the mean.
  3. Leverage the TRIUMPH-2 versus TRIUMPH-1 cross-trial comparison to quantify the weight-mediated glycemic contribution at matched dose levels.
  4. Incorporate dose escalation timing as a covariate in PK-PD models to account for exposure-dependent receptor desensitization.
  5. Validate preclinical models against the Phase 3 dose-response ladder before extrapolating to novel endpoints.

The depth of available Phase 3 data makes retatrutide a uniquely powerful reference compound for integrated glycemic and metabolic research model design in 2026.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-diabetes-data-designing-research-models-around-a1c-glucose-e.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-08 13:11:152026-10-08 13:11:15Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation
Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements

Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements

October 7, 2026/0 Comments/in Uncategorized/by

Nearly half of all participants in major semaglutide trials report nausea, yet weight loss outcomes remain robust even in those who never feel sick. That gap between symptom prevalence and therapeutic outcome sits at the heart of a critical methodological challenge: when ondansetron is co-prescribed to manage GLP-1-associated nausea, do researchers risk blurring the very endpoints they are trying to measure?

Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements is not just a pharmacology question. It is a study-design question that shapes how reliably investigators can attribute changes in food intake, body weight, and gastric motility to the GLP-class agent itself.

Key Takeaways

  • GLP-1 receptor agonists slow gastric emptying through peripheral and central mechanisms that are distinct from the pathways that cause nausea.
  • Ondansetron reduces subjective nausea by blocking 5-HT3 receptors at vagal afferents but does not meaningfully reverse GLP-1-induced gastric stasis.
  • Nausea rates in GLP-1 trials range from roughly 17% to 44%, yet all dose groups produce substantial weight loss, showing that nausea alone does not drive intake reduction.
  • In research settings, ondansetron should be treated as a time-varying covariate, not a confounder of GLP-1 pharmacodynamics on motility or intake.
  • Objective measures such as acetaminophen absorption curves and gastric scintigraphy remain valid even when ondansetron is co-administered.

How GLP-1 Agents Alter Gastric Emptying and Food Intake

GLP-1 receptor agonists act on receptors located in the stomach wall, the duodenum, and the brainstem. The result is a well-documented slowing of gastric emptying that is independent of whether a patient feels nauseated. Semaglutide, for example, delays gastric emptying by roughly 30-40% in the first weeks of therapy. Even after 12 weeks of chronic use, gastric retention remains 10-33% longer than baseline. Gastric scintigraphy and acetaminophen absorption studies consistently confirm this effect.

This motility change matters for intake because food stays in the stomach longer, prolonging satiety signals and reducing how much a person eats at the next meal. Central appetite pathways reinforce that effect. The practical result is that reduced caloric intake on GLP-class drugs reflects both peripheral gastric slowing and central satiety signaling, not nausea-driven food avoidance.

For researchers exploring the GLP-3 peptide signaling pathway and related incretin biology, understanding this mechanistic separation is foundational before any antiemetic covariate is introduced.

How GLP-1 Agents Alter Gastric Emptying and Food Intake


Nausea Prevalence Does Not Equal Mechanism: What Trial Data Show

The pooled STEP trials reported nausea in approximately 42-44% of participants on semaglutide 2.4 mg, compared with roughly 17% on placebo. Tirzepatide trials in the SURPASS and SURMOUNT programs showed nausea rates in the 17-33% range, with a clear dose-response: 24.6% at the lowest dose, rising to 33.3% at mid-dose, then plateauing near 31% at the highest dose. Critically, all dose groups produced substantial and comparable weight loss.

This pattern supports a key conclusion: delayed gastric emptying and central appetite suppression, not nausea per se, are the primary drivers of reduced intake and weight outcomes on GLP-class drugs.

Trial Program Agent Nausea Rate Weight Outcome
STEP (pooled) Semaglutide 2.4 mg ~42-44% Substantial across all groups
SURMOUNT-1 Tirzepatide 5 mg ~24.6% Significant
SURMOUNT-1 Tirzepatide 10 mg ~33.3% Significant
SURMOUNT-1 Tirzepatide 15 mg ~31.0% Significant

Nausea is a real side effect, but it is a parallel signal, not the causal pathway. Researchers reviewing GLP-1 third-generation agents should keep this distinction in mind when designing endpoints.

Nausea Prevalence Does Not Equal Mechanism: What Trial Data Show


Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements in Practice

Ondansetron is now the most commonly prescribed antiemetic for GLP-1-associated nausea in clinical practice, typically at 4-8 mg as needed. It is used in roughly 15-20% of patients during early titration or after dose escalations. Expert reviews consistently frame it as a short-term tolerability tool, not a modifier of the pharmacologic effects on gastric emptying or weight.

Mechanistically, the separation is clean:

  • GLP-1 agents slow gastric emptying via peripheral GLP-1 receptors and central satiety circuits.
  • Ondansetron blocks 5-HT3 receptors at vagal afferents and in the brainstem chemoreceptor trigger zone.
  • These are anatomically and pharmacologically distinct targets.

Clinical data back this up. Small retrospective analyses report roughly 40-65% reductions in nausea scores with 4-8 mg ondansetron in GLP-1-treated patients, yet objective gastric-emptying measures remain persistently delayed. Case reports of semaglutide-induced gastroparesis managed with intravenous ondansetron describe improved symptom tolerance but continued motility impairment on imaging.

Preclinical work adds nuance: in a musk shrew model, exendin-4-induced emesis was not blocked by ondansetron, suggesting that GLP-1-triggered vomiting does not rely exclusively on 5-HT3 pathways. Human patients still benefit clinically, but this finding reinforces the conceptual gap between GLP-1 emetic circuitry and the peripheral motility changes that drive intake reduction.

"Ondansetron addresses the symptom without counteracting the therapeutic mechanism", a principle that should anchor how researchers handle antiemetic co-exposure in GLP-class studies.

For broader context on how peptide mechanisms interact across systems, the Peptides 101 resource for research-use buyers provides useful background on receptor-level distinctions.


Research Design: Treating Ondansetron as a Covariate, Not a Confounder

Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements demands a clear methodological response. As of 2026, no large randomized trial has tested ondansetron for GLP-1 nausea with prespecified gastric-emptying or caloric intake endpoints. Most current evidence comes from retrospective analyses and practice guidelines. That gap creates practical obligations for investigators.

Recommended research-design steps:

  1. Document antiemetic use prospectively, record dose, timing, and duration for every participant.
  2. Assign ondansetron as a time-varying covariate in statistical models, not a fixed group variable.
  3. Use objective gastric-emptying measures, acetaminophen absorption curves or scintigraphy, rather than relying on self-reported fullness.
  4. Record caloric intake independently using validated dietary recall or direct observation, not nausea-behavior proxies.
  5. Monitor GI motility endpoints separately, ondansetron can worsen constipation in patients already prone to bowel slowing on GLP-1 agents, making stool frequency a necessary secondary endpoint.

That last point deserves emphasis. A 2026 clinical commentary specifically cautions that ondansetron may exacerbate GLP-1-related constipation, recommending non-pharmacologic alternatives such as hydration, fiber, and ginger when bowel slowing threatens adherence. For any study tracking broader GI motility, ondansetron use becomes a meaningful covariate, not just for nausea, but for the full motility picture.

Researchers also interested in how peptide combinations affect tolerability profiles can review data on cagrilintide and retatrutide as examples of multi-mechanism agents where covariate management becomes even more complex.

No clinically significant pharmacokinetic interaction between ondansetron and semaglutide or other major GLP-1 agents has been identified through mid-2026, and weight-loss or glucose-lowering efficacy appears unchanged when ondansetron is co-prescribed. This strengthens the case for treating it as a symptom-control covariate rather than a variable that alters GLP-1 pharmacodynamics.

Research Design: Treating Ondansetron as a Covariate, Not a Confounder


Looking Ahead: What Future Studies Need to Resolve

As of 2026, no GLP-1-specific antiemetic has reached phase 3 trials. Growing clinical use of GLP-class agents, including newer agents discussed in resources on GLP-1 reta formulations, is expected to drive development of nausea-targeted adjuncts that modulate GLP-1 emetic pathways without touching gastric emptying or appetite suppression.

Future trials are anticipated to randomize participants to antiemetic versus placebo arms while measuring gastric-emptying times, caloric intake, and weight outcomes in parallel. That design would finally provide definitive data on whether ondansetron or its successors can be used in GLP-class research without confounding mechanistic endpoints.

Until then, the available evidence strongly supports a working framework: ondansetron modifies symptom perception, not gastric-emptying kinetics. Researchers who document its use carefully and apply appropriate statistical controls can preserve the integrity of their motility and intake measurements.


Conclusion

The core finding is straightforward: ondansetron reduces nausea through 5-HT3 receptor blockade at vagal afferents, while GLP-1 agents slow gastric emptying through a separate set of peripheral and central receptors. These mechanisms do not meaningfully overlap, and current evidence confirms that gastric stasis persists even when nausea is well controlled.

Actionable next steps for researchers and clinicians in 2026:

  • Pre-register antiemetic use as a time-varying covariate in any GLP-class study that includes gastric-emptying or caloric intake endpoints.
  • Use objective motility measures, not patient-reported nausea, as primary evidence of GLP-1 pharmacodynamic activity.
  • Track constipation and broader GI motility separately, since ondansetron can compound bowel slowing already induced by GLP-1 agents.
  • Advocate for randomized antiemetic sub-studies embedded within larger GLP-class trials to close the current evidence gap.

Separating what ondansetron does from what GLP-class agents do is not merely an academic exercise. It is the methodological foundation that makes gastric-emptying and intake data trustworthy, and that makes the science of GLP-class research credible.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/ondansetron-in-glp-class-research-separating-antiemetic-effects-from-gastric-emp.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-07 13:04:192026-10-07 13:04:19Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements
Page 1 of 3123
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top