Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: growth hormone releasing hormone

Tesamorelin Research in 2026: What New Visceral-Fat Evidence Means for Body-Composition Study Design

Tesamorelin Research in 2026: What New Visceral-Fat Evidence Means for Body-Composition Study Design

September 24, 2026/0 Comments/in Uncategorized/by

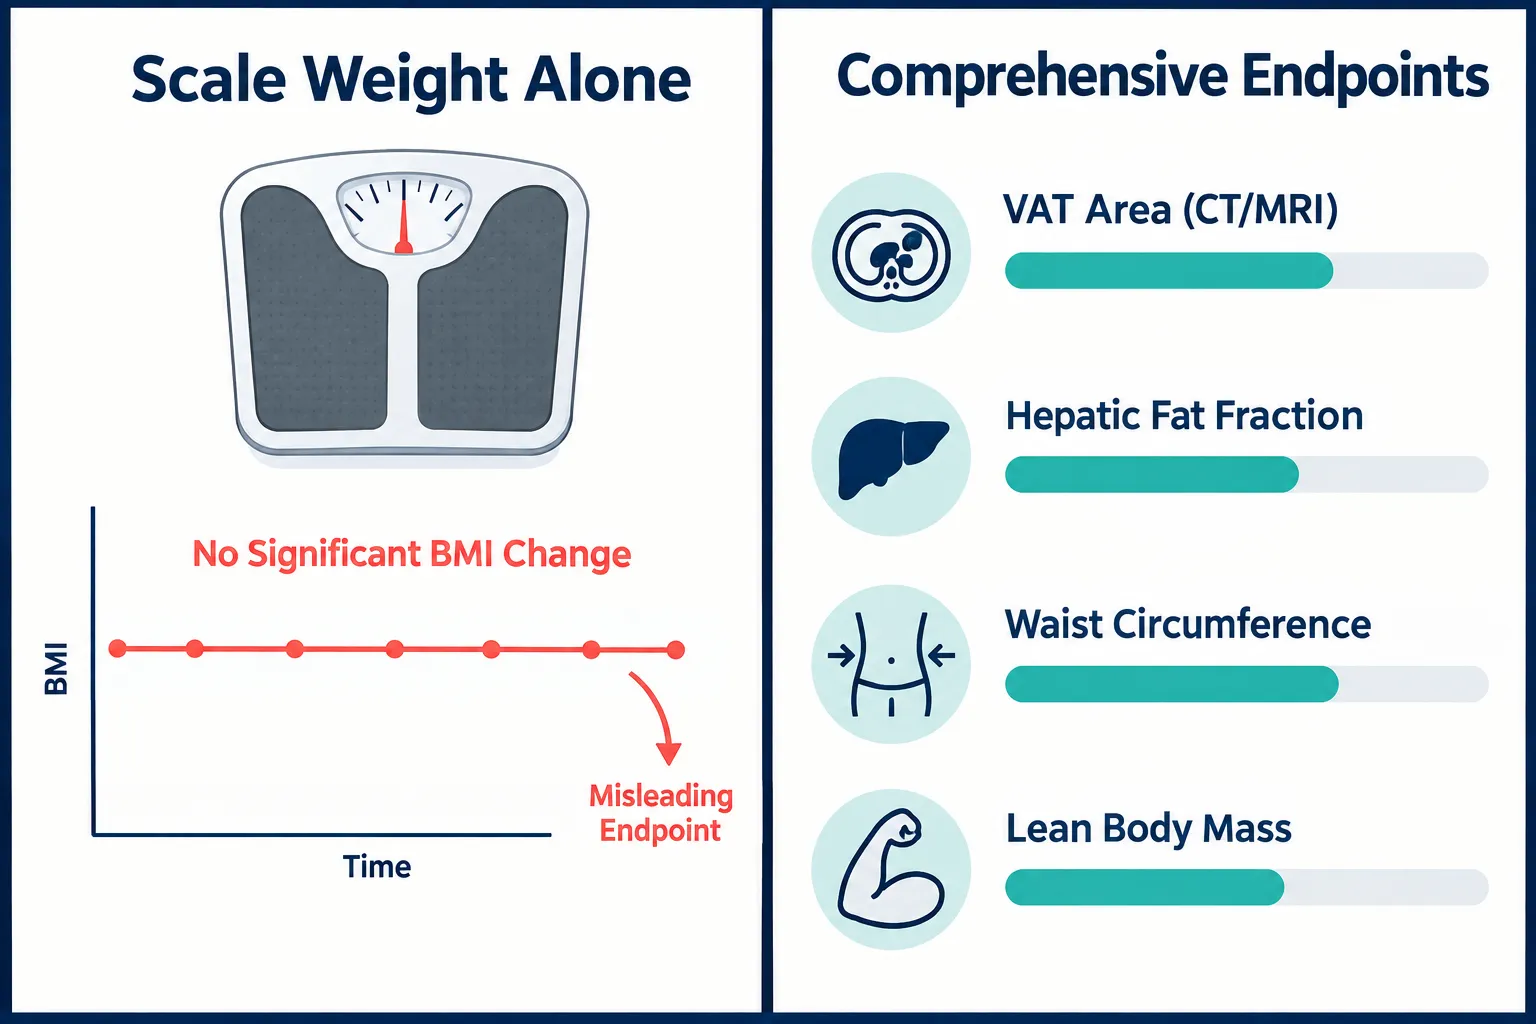
Scale weight has never been a reliable proxy for metabolic health, and the latest evidence on tesa makes that clearer than ever. A 2026 meta-analysis pooling five randomized controlled trials found that tesa reduced visceral adipose tissue by a mean of 27.71 cm² versus placebo, yet produced no significant change in BMI. That single finding reframes how researchers should design body-composition studies and which endpoints actually matter. Tesamorelin Research in 2026: What New Visceral-Fat Evidence Means for Body-Composition Study Design is no longer just a niche HIV pharmacology question, it is a blueprint for the next generation of metabolic trials.

Key Takeaways

  • A 2026 meta-analysis confirms tesa reduces visceral adipose tissue by roughly 27.71 cm² versus placebo with no meaningful BMI change, proving scale weight is an inadequate primary endpoint.
  • Hepatic fat fraction, waist circumference, and lean body mass must be incorporated as secondary endpoints in future body-composition trials.
  • Trials should be designed for at least 24 to 26 weeks of active treatment at a standardized 2 mg daily dose to capture clinically meaningful VAT changes.
  • Categorical "responder" endpoints, such as achieving a threshold reduction in visceral fat, add statistical and clinical value beyond mean differences alone.
  • Tesamorelin remains FDA-approved only for HIV-associated lipodystrophy; evidence in non-HIV populations is still emerging, with NAFLD and cardiometabolic risk reduction as the most plausible areas for future label expansion.

How Tesamorelin Acts on Visceral and Ectopic Fat

Tesamorelin is a synthetic analogue of growth hormone-releasing hormone (GHRH). It binds to GHRH receptors in the pituitary gland, stimulating pulsatile growth hormone secretion, which in turn elevates insulin-like growth factor 1 (IGF-1). This hormonal cascade preferentially mobilizes visceral adipose tissue, the metabolically active fat surrounding internal organs, rather than subcutaneous fat, which explains why total body weight changes little even when internal fat depots shrink substantially.
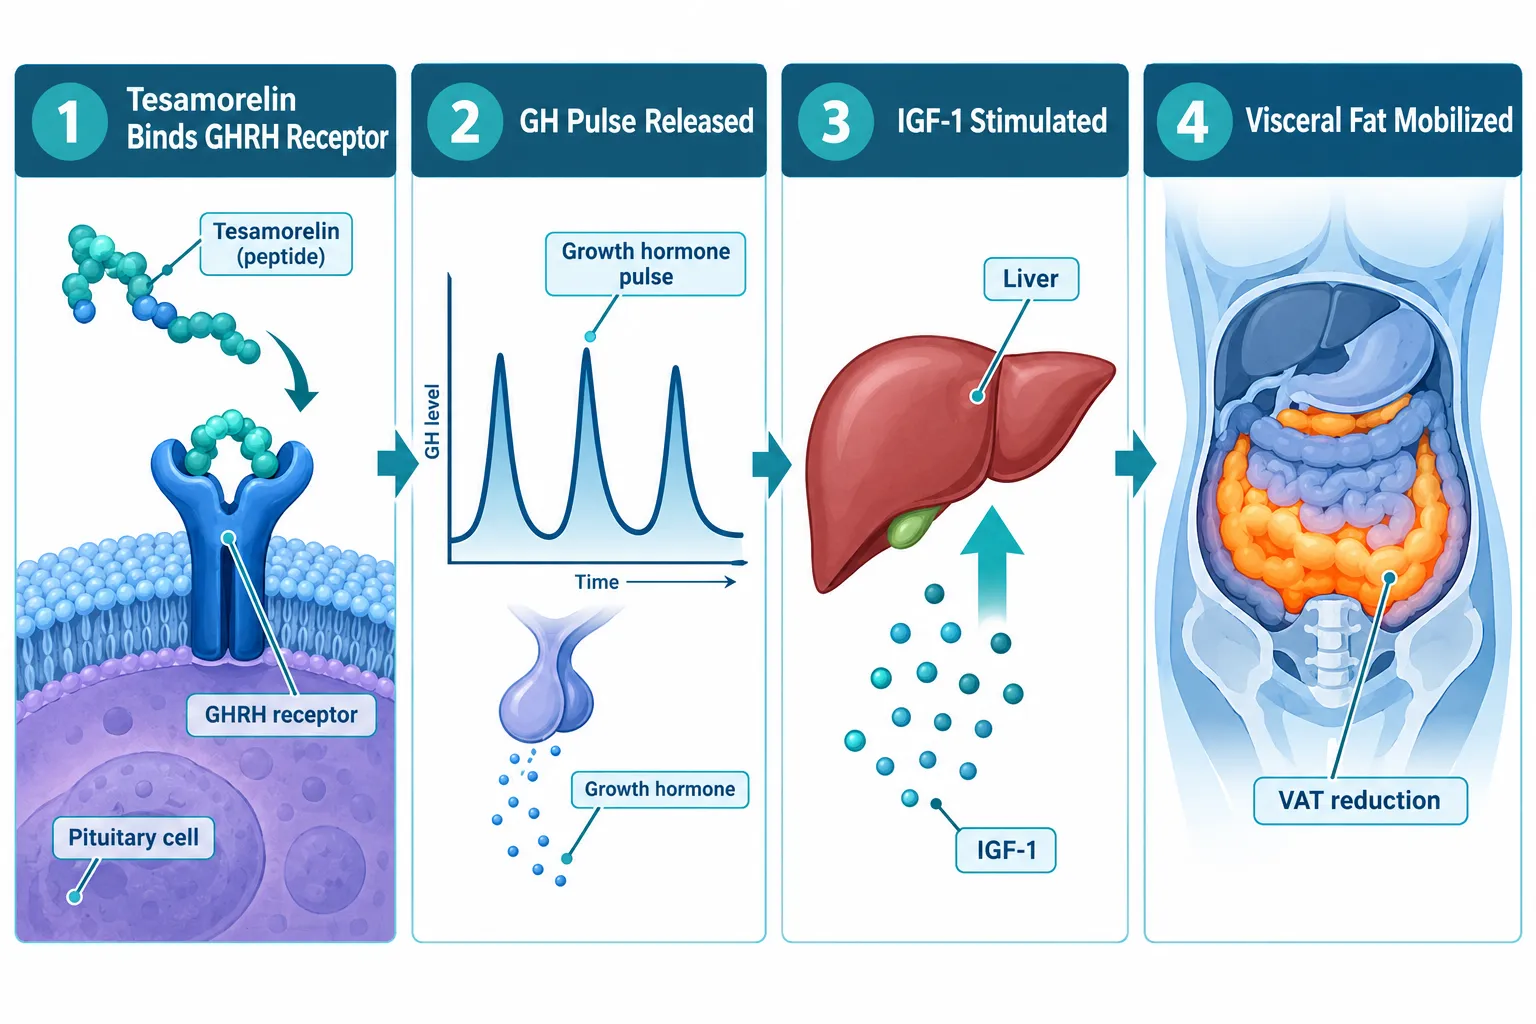
How Tesamorelin Acts on Visceral and Ectopic Fat

This selectivity has important implications. Researchers comparing tesa vs ipamorelin note that each peptide operates through related but distinct pathways, producing different body-composition profiles. Understanding tesa's specific mechanism helps justify why imaging-based endpoints, not scale weight, must anchor future study designs.

Key fat depots affected by tesa:

Depot Direction of Change Magnitude (Pooled Data)
Visceral adipose tissue (VAT) Decrease ~15-28 cm² reduction
Hepatic fat fraction Decrease ~4.2-4.28 percentage points
Trunk fat Decrease Moderate
Waist circumference Decrease ~1.61 cm
Lean body mass Increase ~1.42 kg
BMI No significant change —

The liver fat data deserve particular attention. In people with HIV and nonalcoholic fatty liver disease, tesa has been shown to reduce liver fat content and slow progression of liver inflammation and fibrosis. This positions hepatic fat fraction as a critical secondary endpoint in ongoing and future trials, one that carries direct clinical relevance far beyond cosmetic fat reduction.


What the 2026 Evidence Signals for Study Design

Tesamorelin Research in 2026: What New Visceral-Fat Evidence Means for Body-Composition Study Design converges on a clear methodological message: composite, imaging-based endpoint packages outperform single-metric approaches.

The 2026 meta-analysis reported a 4.28 percentage-point reduction in hepatic fat alongside the VAT reduction. A 2024 randomized controlled trial in people with HIV on integrase inhibitor-based antiretroviral therapy added another layer: 67% of tesa recipients achieved the FDA-defined threshold of at least 8% reduction in visceral fat, compared with a much smaller proportion in the placebo group. That categorical "responder" analysis, not just the mean difference, is what translates into clinically actionable findings.

"Trials that report only mean VAT change miss the distribution of response. Knowing that two-thirds of participants crossed a meaningful threshold is far more informative for clinical decision-making."

Earlier phase III data involving approximately 806 participants showed tesa decreased VAT by 15 to 18% over 26 to 52 weeks, while placebo groups saw VAT increase or remain stable. In one pivotal study, VAT fell 15.2% in the tesa arm but rose 5.0% with placebo, with parallel improvements in triglycerides and total/HDL cholesterol ratios. These consistent effect sizes now anchor power calculations for modern study designs.
What the 2026 Evidence Signals for Study Design

Recommended endpoint package for future trials:

  • Primary: VAT area measured by CT or MRI
  • Secondary: Hepatic fat fraction, waist circumference, lean body mass
  • Exploratory: Triglycerides, total/HDL cholesterol ratio, insulin sensitivity markers
  • Categorical: Proportion achieving threshold VAT or hepatic fat reduction

Researchers planning protocols can consult a tesa dosage calculator to standardize dosing parameters, and review tesa dosage for fat loss frameworks when designing intervention arms.


Practical Implications for Future Body-Composition Trials

The operational requirements of tesa research shape what is feasible in study design. Daily subcutaneous injections, medical evaluation, and ongoing metabolic monitoring are non-negotiable components. These constraints favor trials in motivated, closely followed cohorts with clear metabolic indications, not broad, lifestyle-focused samples.

Practical Implications for Future Body-Composition Trials

Minimum design standards supported by current evidence:

  1. Duration: At least 24 to 26 weeks of active treatment; 12-month data from a 404-patient HIV trial confirm that meaningful VAT changes require sustained therapy.
  2. Dosing: Standardized at 2 mg daily subcutaneous injection where regulatory and safety constraints allow.
  3. Imaging: CT or MRI for VAT area and hepatic fat fraction; waist circumference as a low-cost supplement.
  4. Metabolic monitoring: Glucose, insulin, and lipid panels at baseline, midpoint, and endpoint, especially critical in non-HIV populations where safety profiles are less established.
  5. Population clarity: Current evidence base is overwhelmingly from HIV-associated lipodystrophy cohorts; non-HIV trials require conservative inclusion criteria.

Outside HIV, tesa is now being formally tested in obese individuals with NAFLD in ongoing Phase II randomized, double-blind, placebo-controlled trials registered in 2026. These studies use liver fat reduction as the primary endpoint and include cardiovascular and metabolic secondary outcomes, a design philosophy that reflects the broader shift toward organ-specific fat and risk-marker composites rather than weight loss per se.

For researchers exploring combination peptide protocols, the tesa CJC-1295 ipamorelin 12mg blend represents an area of active investigation, though standalone tesa data remain the gold standard for visceral fat endpoint validation. Those seeking foundational context on peptide mechanisms can also review Peptides 101 for research-use only buyers for structural and mechanistic background.

It is equally important to note what the evidence does not support. Authoritative regulatory and fact-check sources in 2026 reiterate that tesa is FDA-approved only for reducing excess abdominal fat in adults with HIV-associated lipodystrophy and is explicitly not indicated for weight loss management. Evidence in non-HIV patients and in general obesity remains minimal, and off-label use for cosmetic or routine weight loss is not supported by current data. Analysts view NAFLD and cardiometabolic risk reduction, not cosmetic obesity, as the most plausible future areas for label expansion, contingent on results from current Phase II trials.


Conclusion

The 2026 visceral-fat evidence base for tesa delivers a direct challenge to body-composition researchers: stop anchoring studies to scale weight and start building endpoint packages that reflect where the metabolic action actually occurs. VAT area, hepatic fat fraction, waist circumference, and lean body mass together tell a story that BMI simply cannot.

Actionable next steps for research teams:

  • Adopt CT or MRI-based VAT measurement as the primary endpoint in any new tesa protocol.
  • Add hepatic fat fraction and lean body mass as pre-specified secondary endpoints.
  • Power trials for at least 24 to 26 weeks with standardized 2 mg daily dosing.
  • Include categorical responder analyses alongside mean-difference statistics.
  • Restrict non-HIV study populations to those with clear metabolic indications and build in rigorous glucose, insulin, and lipid monitoring from the outset.

Tesamorelin Research in 2026: What New Visceral-Fat Evidence Means for Body-Composition Study Design ultimately points toward a more precise, organ-specific, and metabolically meaningful research paradigm, one where the question is not "how much does the patient weigh?" but "where is the fat, how much of it is dangerous, and is it responding?"
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/tesa-research-in-2026-what-new-visceral-fat-evidence-means-for-body-compo.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-24 13:04:422026-09-24 13:04:42Tesamorelin Research in 2026: What New Visceral-Fat Evidence Means for Body-Composition Study Design

Tag Archive for: growth hormone releasing hormone

Polypeptide Peptides in Endocrine and Metabolic Pathways: How GLP‑3, GLP‑2‑T, and CJC‑1295 Drive Hormone Research

July 7, 2026/0 Comments/by Pure Tested

Fewer than 30 amino acids separate a simple dipeptide from a full-length polypeptide hormone, yet that structural gap represents decades of endocrinology research and some of the most consequential therapeutic discoveries in modern medicine. The phrase "polypeptide peptides" is technically redundant, but it reflects a real gap in how researchers, students, and clinicians talk about these molecules. Understanding that gap is the first step toward grasping how compounds like GLP-3, GLP-2-T, and CJC-1295 are reshaping endocrine and metabolic science in 2026.

This article clarifies the structure-function basics of polypeptide hormones, then maps those principles onto three research-stage peptides that are generating significant scientific interest.

Key Takeaways

  • All peptide hormones are polypeptides, but the term "polypeptide peptides" is often used loosely to describe multi-chain signaling molecules derived from larger precursor proteins.
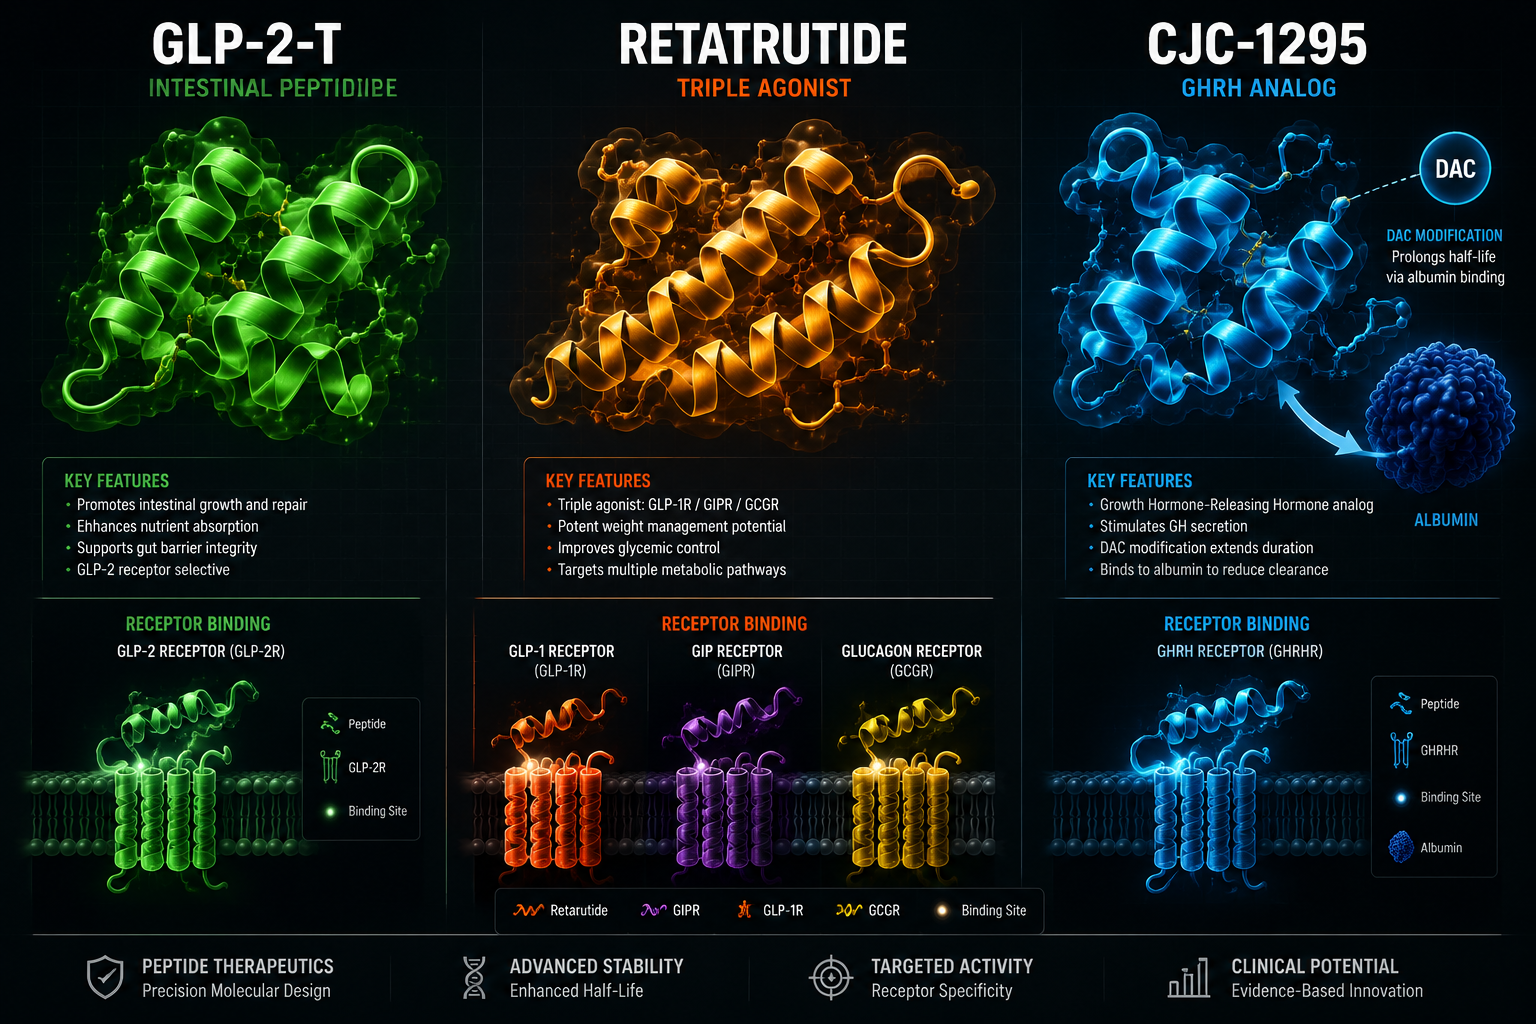
  • GLP-3, GLP-2-T (a stabilized GLP-2 analog), and CJC-1295 each act on distinct receptor systems, incretin, intestinal trophic, and growth hormone-releasing pathways respectively.
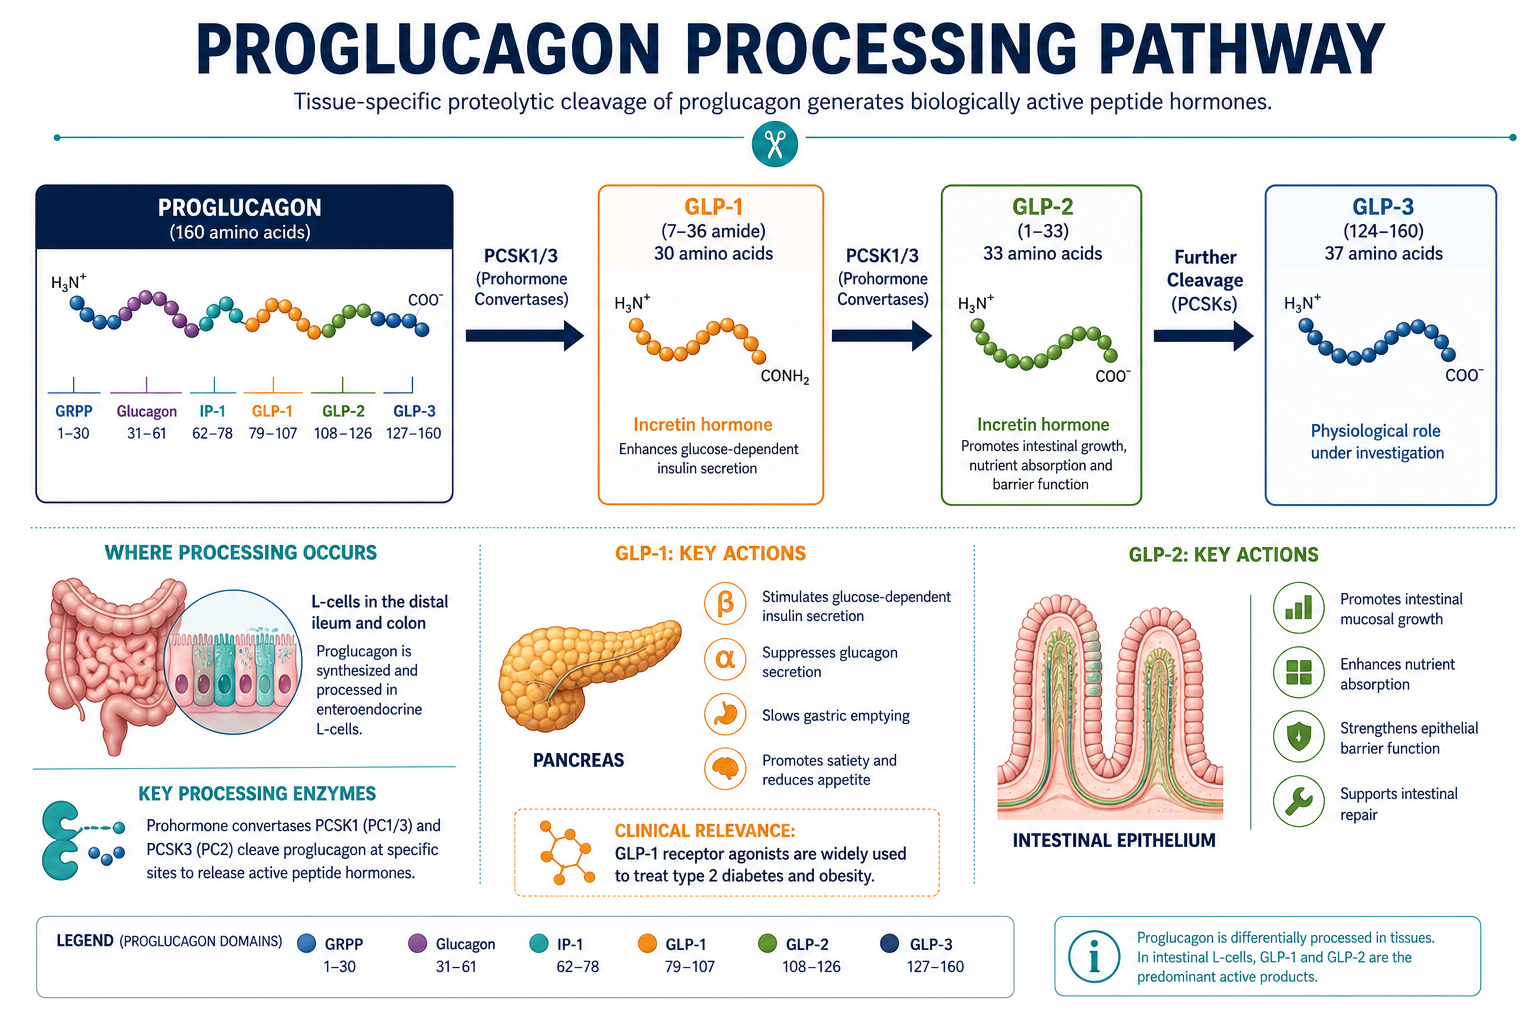
  • Proglucagon is the shared precursor for GLP-1, GLP-2, and GLP-3, with tissue-specific enzyme processing determining which hormone is produced.
  • CJC-1295 extends its half-life through covalent albumin binding, making it a useful model for studying sustained growth hormone axis stimulation.
  • All three compounds are currently restricted to preclinical and research contexts; none are approved for general clinical use.

Key Takeaways

What "Polypeptide Peptides" Actually Means in Endocrine Science

A peptide is any chain of amino acids linked by peptide bonds. A polypeptide is simply a longer chain, conventionally above 10 amino acids. In endocrinology, most signaling hormones fall into this polypeptide range, including insulin, glucagon, and the glucagon-like peptides. When researchers use the phrase "polypeptide peptides in endocrine and metabolic pathways," they are usually describing these multi-residue signaling molecules that bind to G-protein-coupled receptors (GPCRs) to regulate metabolism, growth, and energy balance.

Why does the distinction matter? Because the length and folding of a polypeptide chain determine receptor selectivity, enzymatic stability, and pharmacokinetic behavior. Small modifications, a single amino acid substitution or the addition of a fatty acid chain, can shift a rapidly degraded native peptide into a research-grade compound with a half-life measured in days rather than minutes.

The Proglucagon Precursor: One Gene, Multiple Hormones

Glucagon, GLP-1, GLP-2, and GLP-3 all derive from a single precursor protein called proglucagon. Tissue-specific prohormone convertases (PC2 in the pancreatic alpha cells, PC1/3 in intestinal L-cells) cleave proglucagon at different sites, producing distinct hormones with distinct roles.

  • Glucagon: raises blood glucose; produced in the pancreas
  • GLP-1: stimulates insulin secretion; produced in the gut and brain
  • GLP-2: promotes intestinal mucosal growth and nutrient absorption
  • GLP-3: a less-characterized fragment still under active investigation

For researchers exploring GLP-1 peptide sourcing and generational research concepts, understanding this shared precursor is essential context.


GLP-3 and GLP-2-T: Incretin-Adjacent Peptides in Metabolic Research

GLP-3 and GLP-2-T: Incretin-Adjacent Peptides in Metabolic Research

GLP-3 and the Triple-Agonist Frontier

GLP-3 is a proglucagon-derived fragment whose receptor binding profile is still being characterized. Research interest intensified when it became clear that multi-receptor agonism, hitting GLP-1R, GIPR, and glucagon receptors simultaneously, produces additive metabolic effects. Retatrutide, sometimes discussed in the context of GLP-3 triple-agonist research planning, is a synthetic peptide designed to exploit this multi-agonist principle.

"Multi-receptor agonism represents a shift from single-target pharmacology toward systems-level metabolic intervention, a paradigm that polypeptide research is uniquely positioned to advance."

Proglucagon-derived peptides, including GLP-1 and GIP, regulate energy storage through actions on adipose tissue, influencing white and brown fat activity, islet hormone secretion, and food intake. GLP-3 research extends this framework into less-mapped receptor territory. You can also explore related research on retatrutide and GLP-3 pathway studies for additional context.

GLP-2-T: Stabilized Intestinal Trophic Research

GLP-2-T refers to a stabilized, modified form of GLP-2 designed to resist dipeptidyl peptidase-4 (DPP-4) degradation, the same enzyme that rapidly inactivates native GLP-1 and GLP-2. Native GLP-2 has a half-life of approximately 7 minutes; structural modifications extend this substantially, making it viable for controlled research protocols examining intestinal mucosal integrity, nutrient absorption, and gut barrier function.

The chemical modification strategy mirrors what has been applied to other peptide hormones: amino acid substitutions at DPP-4 cleavage sites, combined in some analogs with fatty acid acylation to enable albumin binding.


CJC-1295 and the Growth Hormone Axis: A Model for Polypeptide Peptides in Endocrine and Metabolic Pathways

Mechanism and Pharmacokinetics

CJC-1295 is a synthetic analog of growth hormone-releasing hormone (GHRH). It binds to GHRH receptors on anterior pituitary somatotrophs, activating the cAMP/PKA signaling pathway. This triggers growth hormone (GH) release and subsequent elevation of insulin-like growth factor 1 (IGF-1).

What makes CJC-1295 a standout research model is its Drug Affinity Complex (DAC) modification. The DAC enables covalent binding to circulating serum albumin, extending the peptide's half-life to approximately 6 to 8 days in humans, compared to minutes for native GHRH. This sustained action allows researchers to study prolonged GH and IGF-1 elevation without repeated dosing.

CJC-1295 underwent Phase II clinical trials for HIV-associated visceral obesity before being discontinued following the death of a trial participant. The death was attributed to pre-existing coronary artery disease and deemed unrelated to the compound, but development did not continue. It remains a research-only compound.

For researchers reviewing CJC-1295 and Ipamorelin assay planning and sourcing, the DAC pharmacokinetics are a central variable in experimental design. Multi-peptide blend studies, such as those examining Tesamorelin and CJC-1295 combinations, also rely on this extended half-life as a design consideration.

CREB Signaling: The Downstream Pathway

CJC-1295's activation of cAMP/PKA feeds into the CREB (cAMP response element-binding protein) transcriptional pathway. CREB and its co-activators act as sensors for hormonal and metabolic signals, mediating gene transcription involved in glucose metabolism and energy balance. This makes CJC-1295 not just a GH secretagogue but a tool for studying broader hormonal gene regulation.

Researchers interested in growth hormone-axis peptides may also find value in reviewing Tesamorelin peptide research, another GHRH analog with a distinct modification profile and its own clinical data set.

Ipamorelin as a Complementary Research Tool

Ipamorelin is a GH secretagogue receptor (GHSR) agonist that stimulates GH release through a different receptor than CJC-1295. Used together in research models, they provide a dual-pathway approach to studying GH axis regulation. Detailed information on Ipamorelin research applications offers useful background for designing multi-peptide studies.


Conclusion

Polypeptide peptides in endocrine and metabolic pathways, from the proglucagon-derived incretin family to synthetic GHRH analogs, represent a structurally diverse but mechanistically coherent class of research tools. GLP-3 and GLP-2-T extend incretin biology into multi-receptor and intestinal trophic territory, while CJC-1295 provides a well-characterized model for sustained growth hormone axis stimulation through albumin-binding pharmacokinetics.

Actionable next steps for researchers:

  • Map the proglucagon processing pathway before designing any GLP-family study to ensure receptor selectivity is clearly defined.
  • Evaluate DPP-4 stability data when selecting GLP-2-T analogs, as modification sites directly affect experimental half-life.
  • Review CJC-1295 DAC pharmacokinetics and CREB pathway literature before establishing dosing intervals in GH-axis protocols.
  • Source peptides from suppliers with documented purity standards; consult peptide supplier comparison resources and reference standard benchmarking guides to validate compound integrity before use.

All compounds discussed here are for preclinical research purposes only and are not approved for human therapeutic use outside of authorized clinical trial frameworks.

https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 0 0 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-07 13:20:052026-07-20 15:00:49Polypeptide Peptides in Endocrine and Metabolic Pathways: How GLP‑3, GLP‑2‑T, and CJC‑1295 Drive Hormone Research
CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Research Studies

CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Research Studies

June 20, 2026/0 Comments/by Pure Tested

}

Professional () hero image with : 'CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release' in extra large white with

A single subcutaneous injection of CJC-1295 produced a 2- to 10-fold increase in mean plasma growth hormone levels lasting up to six days — a finding that reshaped how researchers think about pulsatile GH stimulation. When paired with Ipamorelin, this effect takes on a new dimension entirely. Understanding the science behind CJC-1295 with Ipamorelin: optimizing growth hormone release for research studies requires examining both peptides at the receptor level and then exploring what happens when their pathways converge.

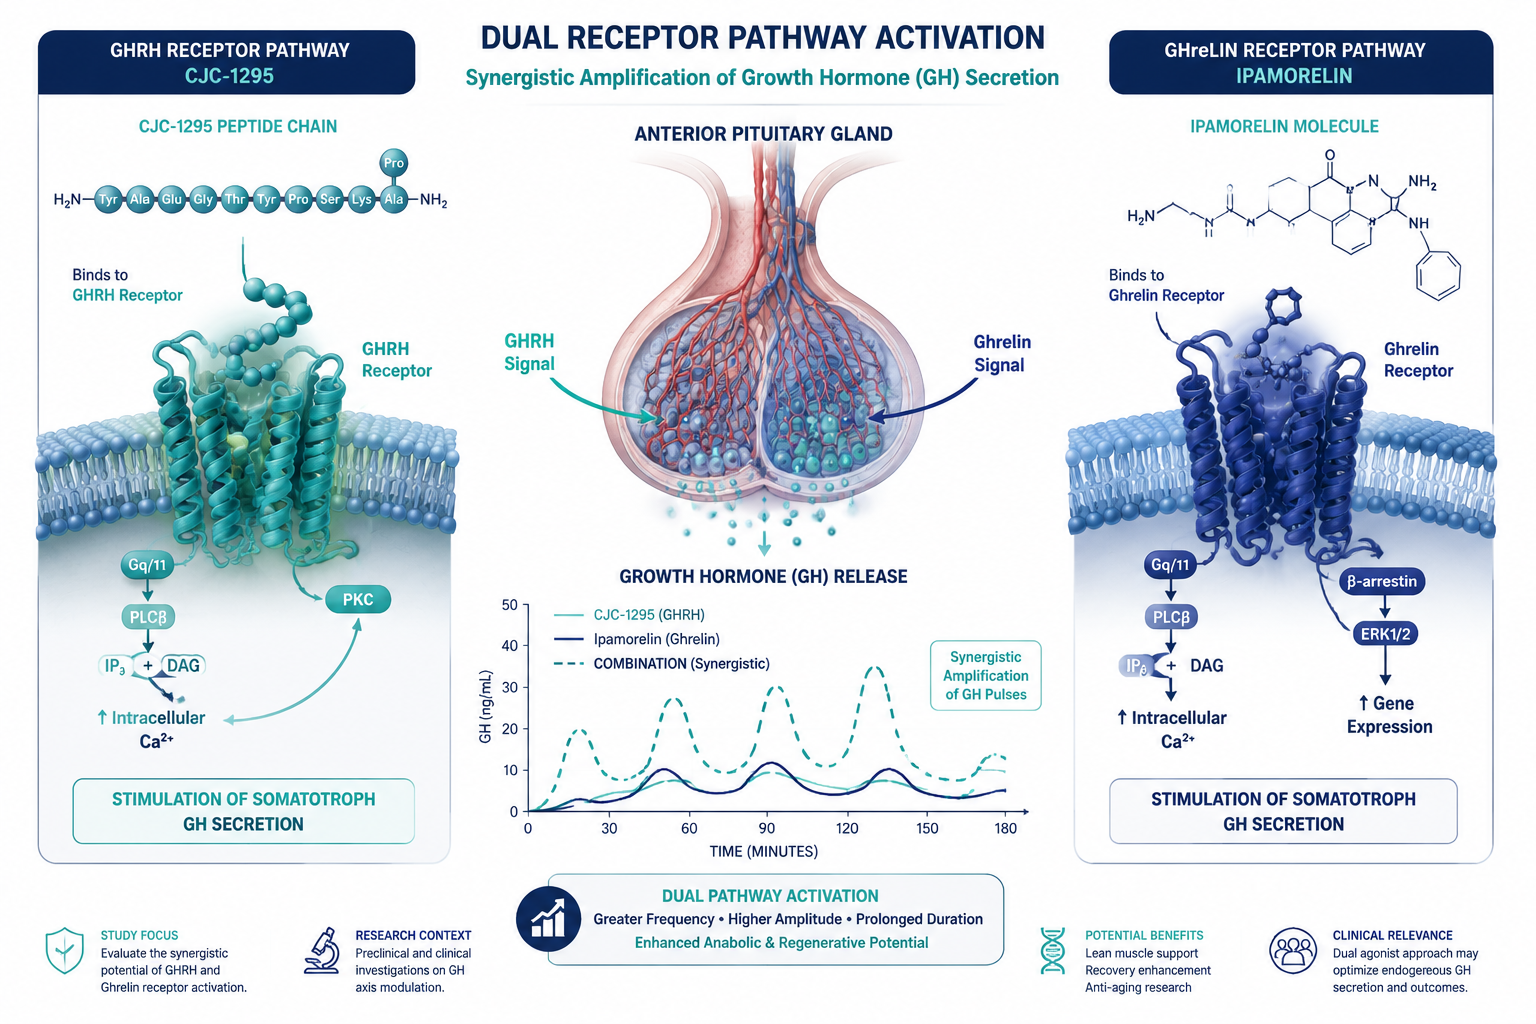
Detailed () scientific diagram illustration showing dual receptor pathway activation: left panel labeled GHRH receptor with

Key Takeaways

  • CJC-1295 is a long-acting GHRH analog; Ipamorelin is a selective ghrelin receptor agonist — they activate distinct GH-release pathways.
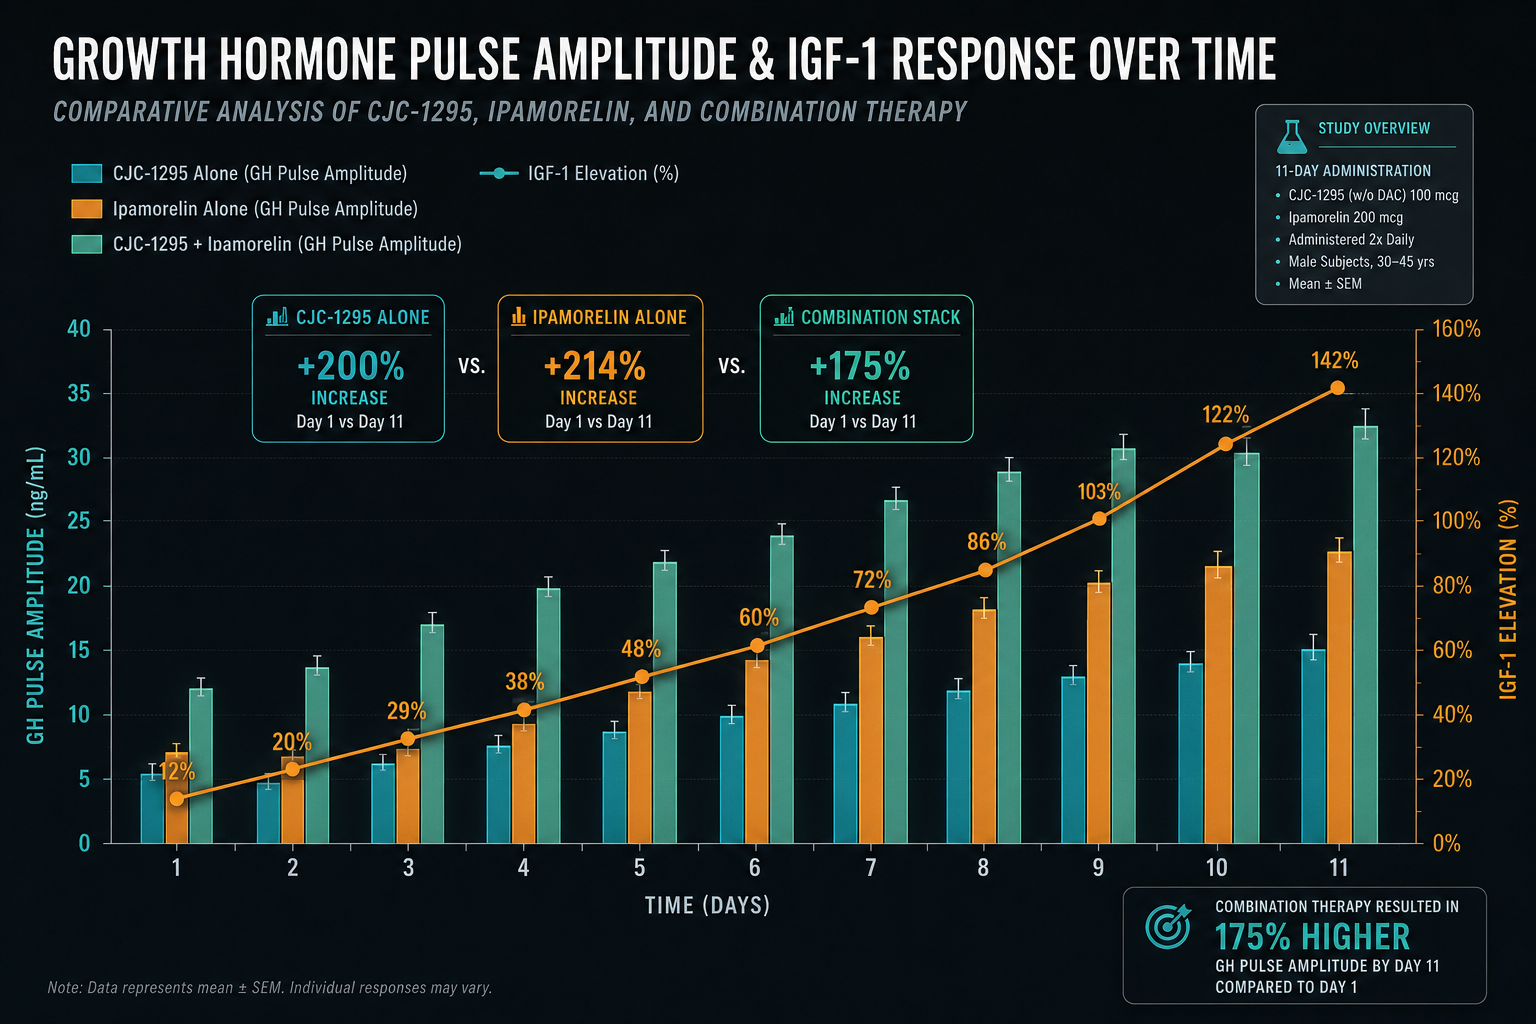
  • Combining both peptides produces greater GH pulse amplitude and frequency than either compound alone.
  • A 2006 clinical study confirmed CJC-1295's extended half-life of 5.8 to 8.1 days and elevated IGF-1 for up to 11 days.
  • Neither peptide is FDA-approved; both are classified as research chemicals and appear on the WADA prohibited list.
  • No published randomized controlled trials exist for the combination as of 2026, making rigorous preclinical study design critical.

Mechanisms Behind the Synergy

CJC-1295 is a modified analog of Growth Hormone-Releasing Hormone (GHRH). It binds to GHRH receptors on the anterior pituitary, signaling somatotroph cells to synthesize and release GH. Its key structural modification — Drug Affinity Complex (DAC) technology — allows it to bind albumin in plasma, dramatically extending its half-life to between 5.8 and 8.1 days. This stands in sharp contrast to sermorelin and CJC-1295 comparisons where sermorelin clears the body in roughly 10 to 12 minutes and tesa in approximately 30 minutes.

Ipamorelin operates through an entirely separate mechanism. It mimics ghrelin by binding to the GHS-R1a receptor, a G-protein-coupled receptor found on pituitary somatotrophs and hypothalamic neurons. Critically, Ipamorelin achieves GH stimulation without meaningfully elevating cortisol or prolactin, which distinguishes it from older secretagogues like GHRP-6 or GHRP-2.

When both peptides are used together, the result is a dual-pathway amplification of GH release. GHRH receptor activation raises the ceiling on GH output, while ghrelin receptor stimulation increases the frequency of GH pulses. Research models studying this combination can explore the CJC-1295 no-DAC research themes alongside full DAC variants to isolate half-life variables.


Clinical Evidence and Research Protocols for CJC-1295 with Ipamorelin

The foundational human data for CJC-1295 comes from a pivotal 2006 study published in the Journal of Clinical Endocrinology and Metabolism. Key findings included:

Parameter Observed Outcome
Plasma GH increase 2- to 10-fold above baseline
Duration of GH elevation Up to 6 days post-injection
IGF-1 increase 1.5- to 3-fold above baseline
IGF-1 elevation duration 9 to 11 days
Estimated half-life 5.8 to 8.1 days
Tolerated dose range 30 to 60 mcg/kg

No serious adverse reactions were observed at these doses. However, no additional human RCTs have been published since 2006, and the CJC-1295/Ipamorelin combination has not been formally tested in published human controlled trials as of 2026.

Clinical Evidence and Research Protocols for CJC-1295 with Ipamorelin

For preclinical research, the combination is typically studied using models that track pulsatile GH secretion patterns over 24-hour windows. Researchers interested in multi-peptide blends can also review tesa, CJC-1295, and Ipamorelin blend protocols to understand how additional GHRH analogs interact within the same framework. A related resource on combining tesa with CJC-1295 and Ipamorelin safety considerations addresses stack-level safety questions relevant to protocol design.

"While CJC-1295 and Ipamorelin can synergistically enhance GH release, their long-term safety and efficacy remain under-researched." — Dr. Quinn Stillson, April 2026


Regulatory Status, Risks, and Research Sourcing

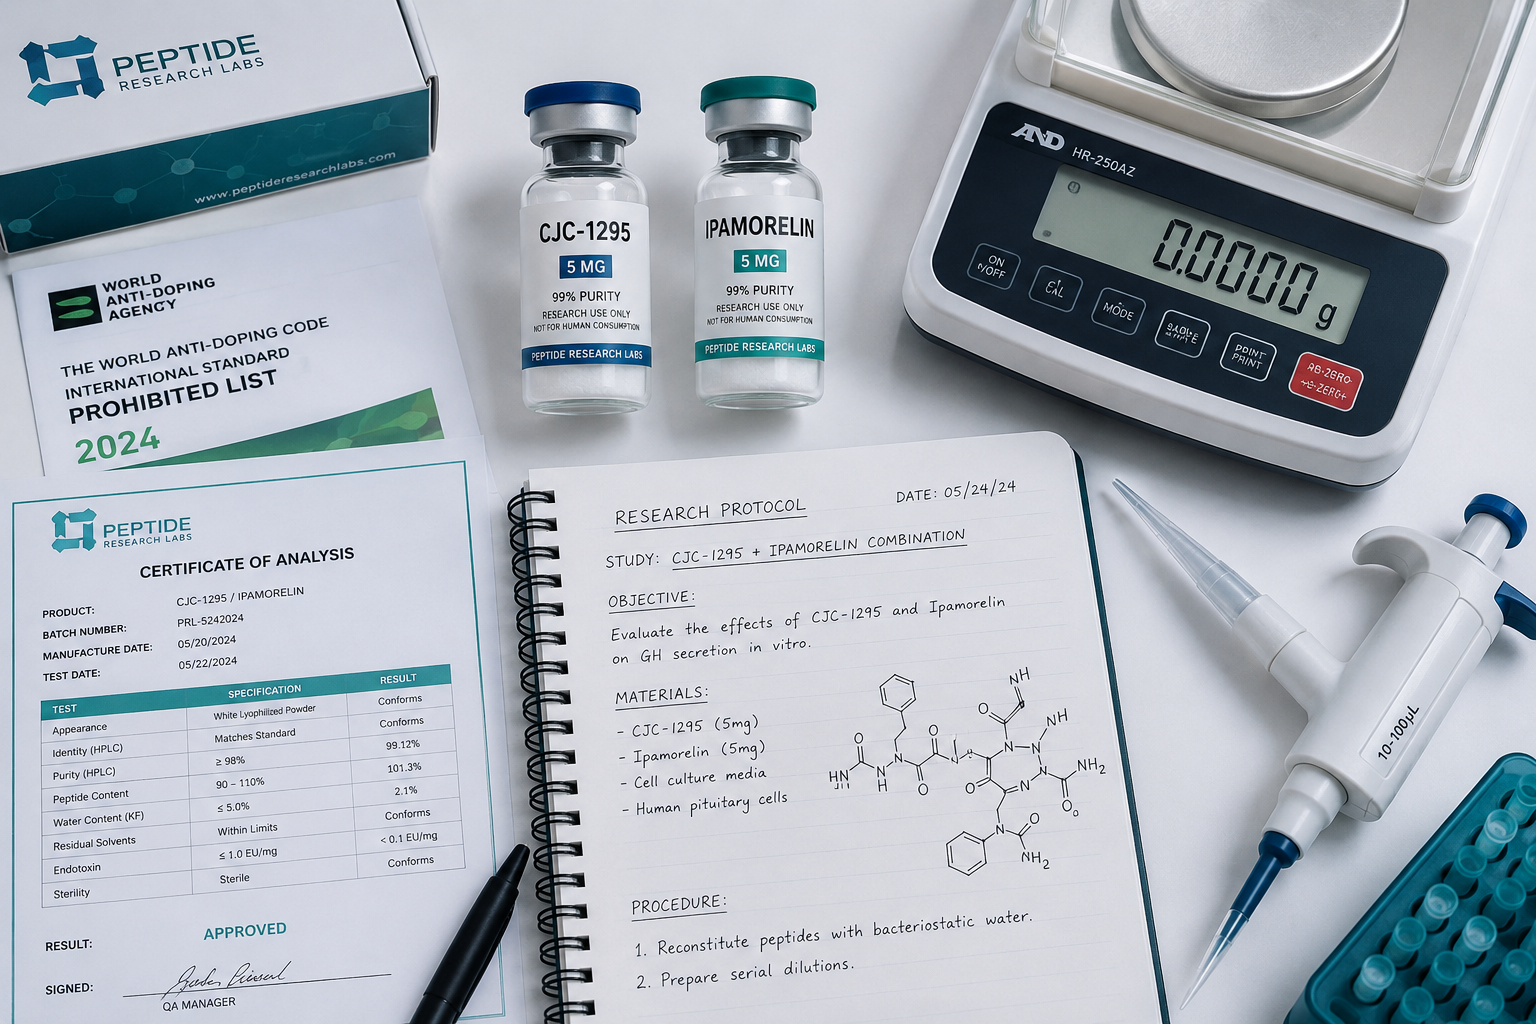
As of 2026, neither CJC-1295 nor Ipamorelin holds FDA approval for any indication. Both are classified as research chemicals for laboratory use only and are listed on the World Anti-Doping Agency's prohibited substances list. This regulatory status has direct implications for study design, institutional review, and sourcing standards.

Key risk considerations for research models include:

  • Potential receptor desensitization with prolonged GH secretagogue exposure
  • Difficulty assessing long-term consequences of sustained elevated IGF-1 without longitudinal human data
  • Variability in peptide purity across suppliers, which can confound results

Sourcing peptides with verified purity documentation is non-negotiable for valid research outcomes. Reviewing certificates of analysis before procurement ensures compound integrity. Researchers building broader metabolic panels may also find value in MOTS-c metabolic flexibility research themes or BPC-157 research themes as complementary study arms.

For those sourcing the combination directly, the CJC-1295 with Ipamorelin 10mg research product provides a pre-blended option with documented testing standards.

Regulatory Status, Risks, and Research Sourcing


Conclusion

CJC-1295 with Ipamorelin: optimizing growth hormone release for research studies represents one of the most mechanistically coherent dual-peptide strategies in current GH research. The GHRH/ghrelin receptor co-activation model offers a compelling framework for studying pulsatile GH dynamics, IGF-1 modulation, and downstream metabolic effects.

Actionable next steps for researchers in 2026:

  1. Define your GH endpoint clearly — pulse amplitude, IGF-1 area under the curve, or downstream tissue response.
  2. Source verified, tested peptides with published certificates of analysis to eliminate purity as a confounding variable.
  3. Design time-course sampling protocols that capture the extended half-life profile of CJC-1295 (up to 11 days for IGF-1 elevation).
  4. Consult current regulatory guidance before initiating any study involving WADA-listed compounds.
  5. Review adjacent peptide research — including Ipamorelin and sermorelin stack research — to contextualize your findings within the broader secretagogue literature.

The data foundation exists. Rigorous, well-sourced research design is what transforms that foundation into meaningful scientific contribution.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/CJC-1295-with-Ipamorelin-Optimizing-Growth-Hormone-Release-for-Research-Studies.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-20 13:03:202026-07-20 15:02:41CJC-1295 with Ipamorelin: Optimizing Growth Hormone Release for Research Studies
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top