

Methylprednisolone, Dexamethasone, and Peptide-Based Immunomodulation: Designing Inflammation Studies With BPC-157 and GLP-Class Adjuncts
Fewer than 15% of preclinical inflammation studies account for pharmacokinetic differences between corticosteroids when adding novel peptide adjuncts, a gap that can invalidate cytokine readouts before data collection even begins. For researchers designing protocols that combine methylprednisolone, dexamethasone, and peptide-based immunomodulation, understanding how each agent interacts at the molecular level is not optional; it is the foundation of reproducible science.
This article maps the current evidence landscape for combining or comparing classic glucocorticoids with tissue-repair peptides such as BPC-157 and GLP-class compounds, with a focus on cytokine endpoints and safety considerations relevant to 2026 laboratory practice.
Key Takeaways
- Methylprednisolone and dexamethasone differ meaningfully in half-life, tissue penetration, and mineralocorticoid activity, which affects how they interact with peptide adjuncts in study designs.
- GLP-1 receptor agonists demonstrate robust, clinically validated anti-inflammatory effects, reducing CRP, TNF-alpha, IL-6, and IL-1beta across multiple trial populations.
- BPC-157 shows promising preclinical cytokine data but remains at an early evidentiary stage with no large randomized trials completed as of mid-2026.
- Combining corticosteroids with immunomodulatory peptides requires stratified dosing and careful timing to avoid overlapping immunosuppressive effects.
- Cytokine panel selection, particularly CRP, TNF-alpha, IL-6, and adiponectin, is critical for detecting both suppressive and pro-resolving signals in multi-agent models.
Corticosteroid Pharmacology: Why Methylprednisolone and Dexamethasone Are Not Interchangeable
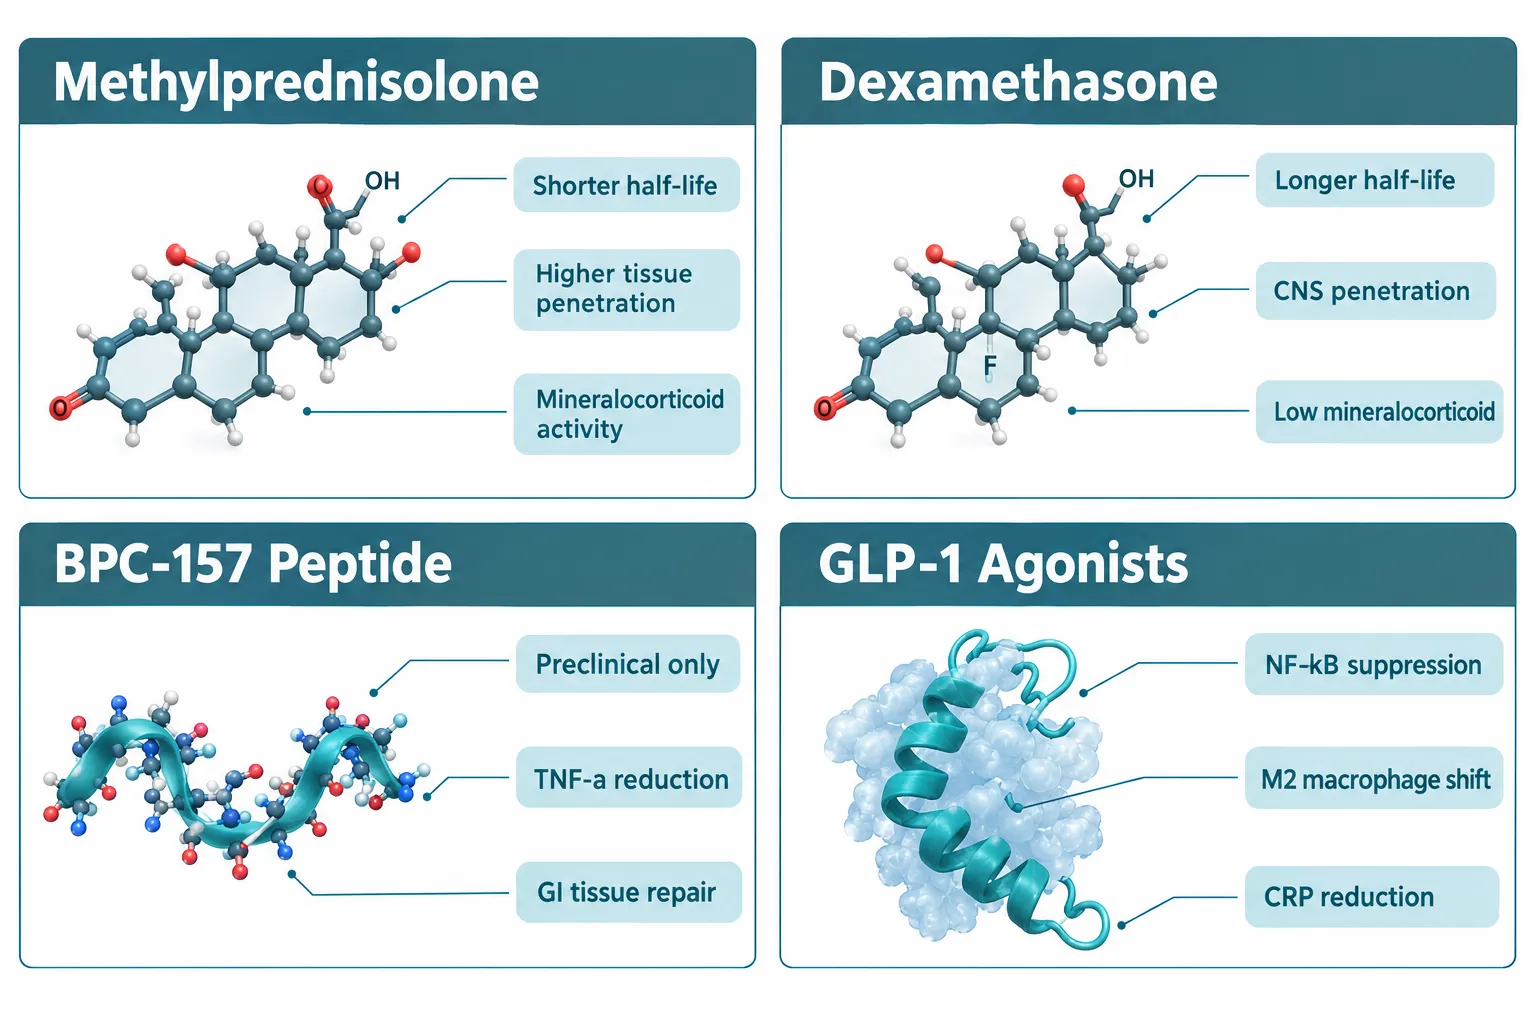
Both methylprednisolone and dexamethasone are synthetic glucocorticoids that suppress inflammation through genomic and non-genomic pathways, but their pharmacological profiles diverge in ways that matter enormously for study design.
Dexamethasone carries a longer biological half-life, superior central nervous system penetration, and negligible mineralocorticoid activity. In 2025 comparative analyses of moderate-to-severe COVID-19 patients, dexamethasone produced faster symptom resolution, shorter hospital stays, and more favorable CRP trajectories than methylprednisolone in certain acute viral-inflammatory contexts.
Methylprednisolone, by contrast, may be preferred in hypoxic pulmonary settings where its distinct tissue-penetration profile and intermediate half-life offer advantages. Clinical analyses published in 2025 specifically support methylprednisolone over dexamethasone in hypoxic COVID-19 patients, reinforcing that optimal steroid selection depends on disease phase and organ involvement, not a single universal hierarchy.
For inflammation studies, the practical differences include:
| Feature | Methylprednisolone | Dexamethasone |
|---|---|---|
| Biological half-life | 18-36 hours | 36-54 hours |
| Mineralocorticoid activity | Low-moderate | Minimal |
| CNS penetration | Moderate | High |
| Dose equivalence (vs. prednisolone) | 0.8x | 0.13x |
GLP-Class Adjuncts: The Evidence Base for Anti-Inflammatory Peptide Immunomodulation
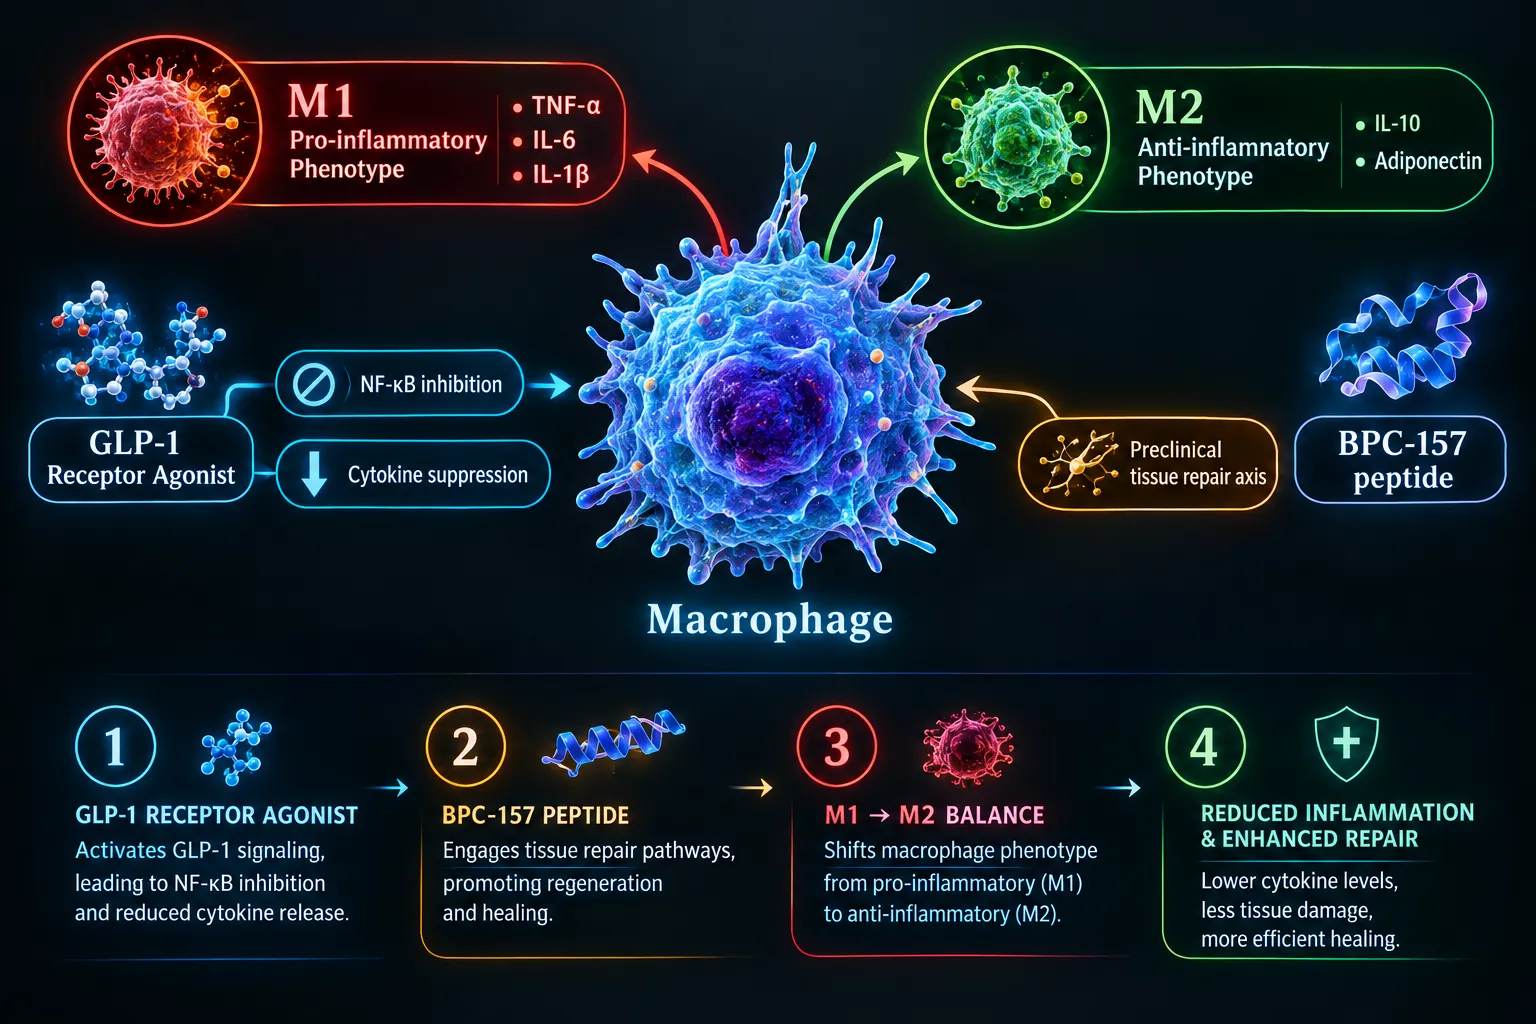
The strongest peptide-level evidence for immunomodulation in 2026 belongs to GLP-1 receptor agonists. A systematic review and meta-analysis of 40 randomized controlled trials, covering more than 6,000 participants with type 2 diabetes, confirmed that GLP-1 receptor agonists significantly reduced key systemic inflammatory biomarkers compared to placebo, insulin, and oral agents.
Quantified effects from a February 2026 meta-analysis include:
- CRP: standardized mean difference of approximately -0.63
- TNF-alpha: approximately -0.92
- IL-6: approximately -0.76
- IL-1beta: approximately -3.89
- Leptin: approximately -0.67
- Adiponectin: increased by approximately +0.69
These are not trivial shifts. The adiponectin increase signals a genuine pro-resolving phenotypic change, not merely cytokine suppression. Mechanistic data compiled through 2025 and 2026 show that GLP-1 receptor agonists promote macrophage M2 (anti-inflammatory) polarization, inhibit M1 (pro-inflammatory) phenotypes, reduce microglial activation, and suppress TNF-alpha, IL-6, IL-1beta, IL-2, IL-17A, and interferon-gamma simultaneously.
Across neurodegenerative and ischemic stroke models, GLP-1 receptor agonists modulate neuroinflammation through a regulatory T-cell to microglia to neuron signaling axis, positioning them as multi-organ immunomodulatory agents rather than purely metabolic drugs. Researchers exploring GLP-3 peptide variants should note that mechanistic overlap with GLP-1 pathways may influence cytokine panel design when these compounds are used alongside corticosteroids.
For labs sourcing research compounds, working with a best peptide supplier that provides verified purity documentation is essential for maintaining data integrity in multi-agent studies. Researchers can also explore GLP-3 peptide for sale options when designing GLP-class adjunct arms. For broader context on how GLP-class peptides compare to small-molecule drugs in metabolic models, see this detailed analysis on polypeptide peptides in cardiometabolic models.
BPC-157 in Inflammation Models: Preclinical Promise, Clinical Caution
BPC-157 occupies a fundamentally different position in the evidence hierarchy. As of mid-2026, only three pilot human studies exist, covering intra-articular knee pain, interstitial cystitis, and an intravenous safety and pharmacokinetics evaluation, all small and non-definitive. No large randomized trials or regulatory approvals for any inflammatory indication have been completed.
Preclinical data, however, are genuinely interesting. BPC-157 markedly reduces TNF-alpha, IL-6, and interferon-gamma in animal models and supports tissue repair in gastrointestinal, vascular, and neural systems. The ongoing safety trial PCO-02 (NCT02637284) continues to evaluate basic safety rather than efficacy, meaning any use of BPC-157 as a corticosteroid adjunct remains experimental and off-label.
Researchers designing studies that combine methylprednisolone, dexamethasone, and peptide-based immunomodulation with BPC-157 should:
- Power the study for preclinical endpoints only until human data mature
- Include full cytokine panels (TNF-alpha, IL-6, IL-1beta, CRP, interferon-gamma)
- Pre-register dosing rationale and timing relative to corticosteroid administration
- Monitor for additive immunosuppressive effects, particularly on interferon-gamma
Labs interested in mitochondria-targeted peptide adjuncts alongside anti-inflammatory protocols may also find value in reviewing SS-31 peptide benefits, given its role in oxidative stress reduction within inflammatory models. Those sourcing compounds for multi-arm studies can explore options to buy SS-31 peptide from verified suppliers. For growth hormone-related peptide adjuncts with documented metabolic and anti-inflammatory overlap, Tesamorelin peptide benefits provide useful comparative context.
Designing Multi-Agent Inflammation Studies: Cytokine Readouts and Safety Considerations
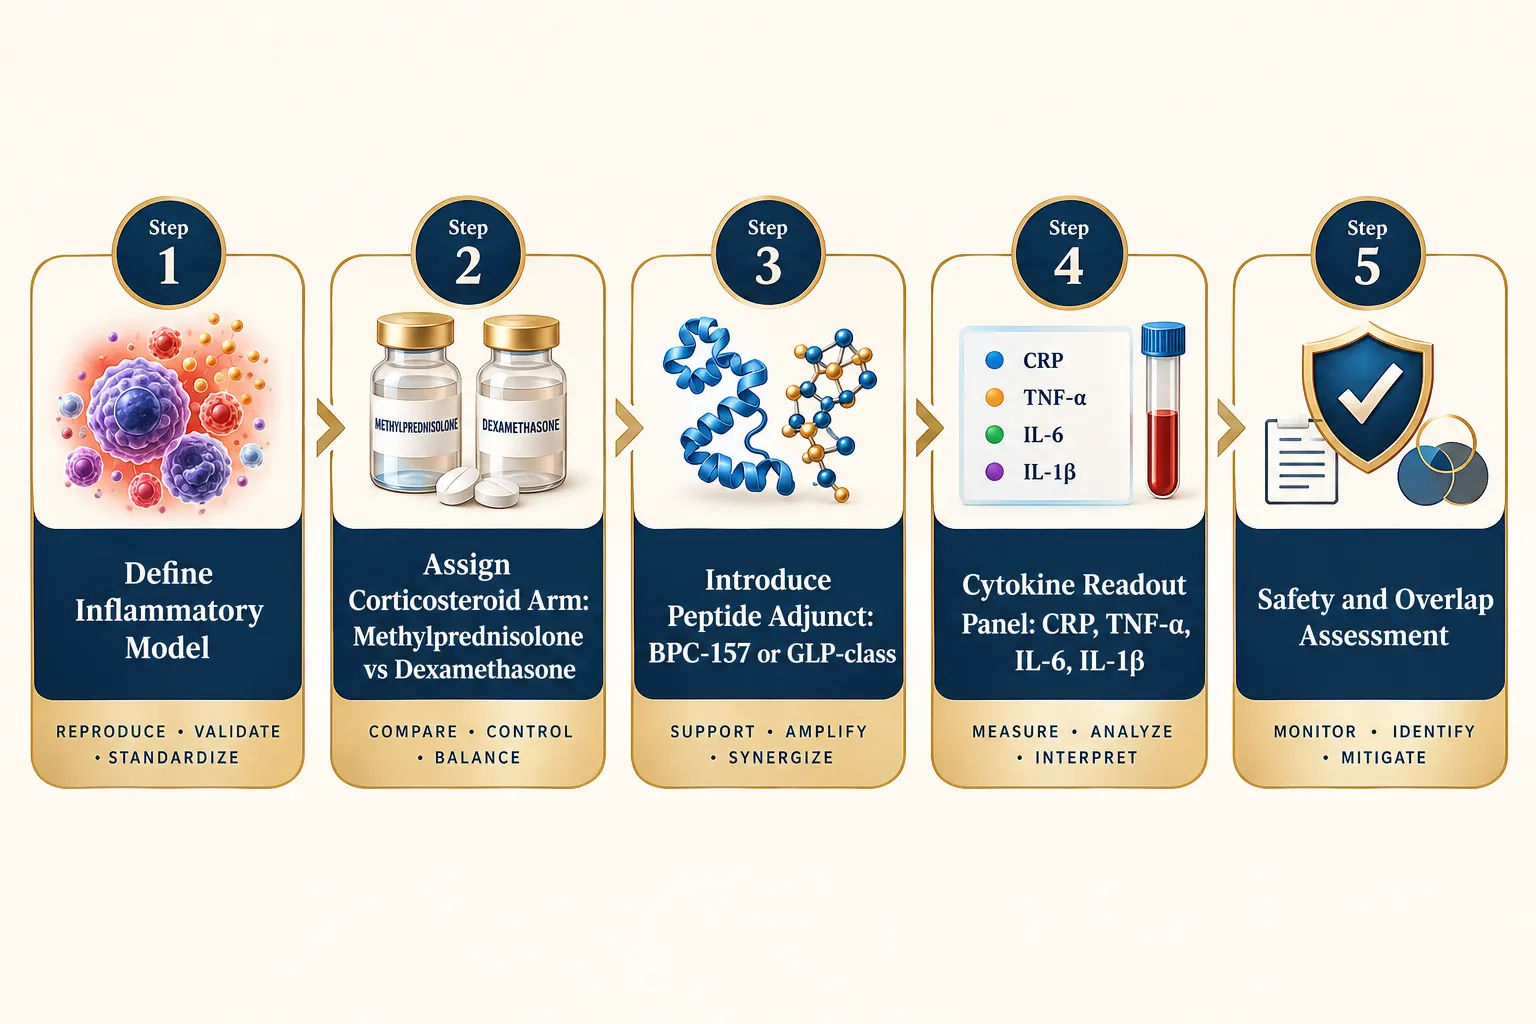
Combining corticosteroids with immunomodulatory peptides introduces compounding variables that can obscure or amplify cytokine signals. The following framework addresses the most common design failures.
Cytokine Panel Minimum Requirements
For studies involving methylprednisolone, dexamethasone, and peptide-based immunomodulation, a minimum cytokine readout panel should include:
- Pro-inflammatory: CRP, TNF-alpha, IL-6, IL-1beta, IL-17A
- Anti-inflammatory/resolving: IL-10, adiponectin
- Immune cell markers: macrophage M1/M2 ratio where feasible
Timing and Overlap Risks
Because dexamethasone has a longer half-life than methylprednisolone, staggered dosing with any GLP-class peptide must account for residual glucocorticoid activity. Overlapping NF-kB suppression from both a corticosteroid and a GLP-1 receptor agonist could mask the peptide's independent contribution to cytokine reduction, producing falsely attributed effect sizes.
Safety Monitoring
GLP-1 receptor agonist therapy has not been shown to increase inflammatory bowel disease exacerbation rates in 2025-2026 analyses, supporting its safety in patients with baseline gut inflammation. BPC-157, however, lacks equivalent safety data at scale, requiring conservative dose escalation protocols in any combination study.
Conclusion
The intersection of methylprednisolone, dexamethasone, and peptide-based immunomodulation represents one of the most methodologically demanding areas in current inflammation research. GLP-class adjuncts now carry a substantial clinical evidence base for cytokine suppression and immune-cell polarization, making them credible candidates for combination study designs with corticosteroids. BPC-157 remains preclinical in scope, requiring careful framing of any multi-agent protocol as exploratory.
Actionable next steps for research teams:
- Audit existing protocols for steroid dose-equivalence errors before adding peptide arms
- Select cytokine panels that capture both suppressive (TNF-alpha, IL-6) and pro-resolving (IL-10, adiponectin) endpoints
- Source compounds from lab tested peptides suppliers with documented purity certificates to protect data validity
- Pre-register BPC-157 combination studies as exploratory to accurately represent the current evidence stage
- Monitor for overlapping NF-kB suppression when combining dexamethasone with GLP-1 receptor agonists in the same arm
Rigorous design at the intersection of classic steroids and emerging peptide immunomodulators will determine whether these combinations advance from promising preclinical signals to validated therapeutic strategies.