

Spironolactone and Peptide Metabolism Studies: Aldosterone, Potassium, Fluid Volume, and Hormonal Readouts
}

Fewer drug mechanisms have remained as consistently relevant to endocrine research as aldosterone antagonism, and yet, as 2026 proteomic studies reveal, the downstream effects of spironolactone extend well beyond simple electrolyte shifts. Researchers designing peptide metabolism studies increasingly encounter spironolactone and peptide metabolism studies: aldosterone, potassium, fluid volume, and hormonal readouts as a methodological framework that demands careful interpretation of multiple, often interdependent biomarkers.
Key Takeaways
- Spironolactone blocks aldosterone at the distal renal tubule, driving sodium and water excretion while retaining potassium.
- Fluid volume reduction is a core, measurable outcome in both clinical and preclinical peptide models.
- Potassium monitoring thresholds (stop/seek advice at greater than 6 mmol/L) remain a critical safety parameter in research protocols.
- 2026 biomarker studies show spironolactone affects hormonal markers such as PICP, GAL9, THBS2, and REN, independent of classic electrolyte changes.
- Interpreting hormonal readouts in peptide experiments requires distinguishing direct aldosterone-antagonist effects from broader RAAS-mediated signaling.
Mineralocorticoid Receptor Antagonism: The Mechanistic Foundation
Spironolactone acts as a specific antagonist of aldosterone at the aldosterone-dependent sodium-potassium exchange site in the distal renal tubule. When aldosterone is blocked, the tubule excretes more sodium and water while retaining potassium. This mechanism, unchanged in the most current U.S. product labeling as of August 2026, forms the backbone of every study design that incorporates this compound.
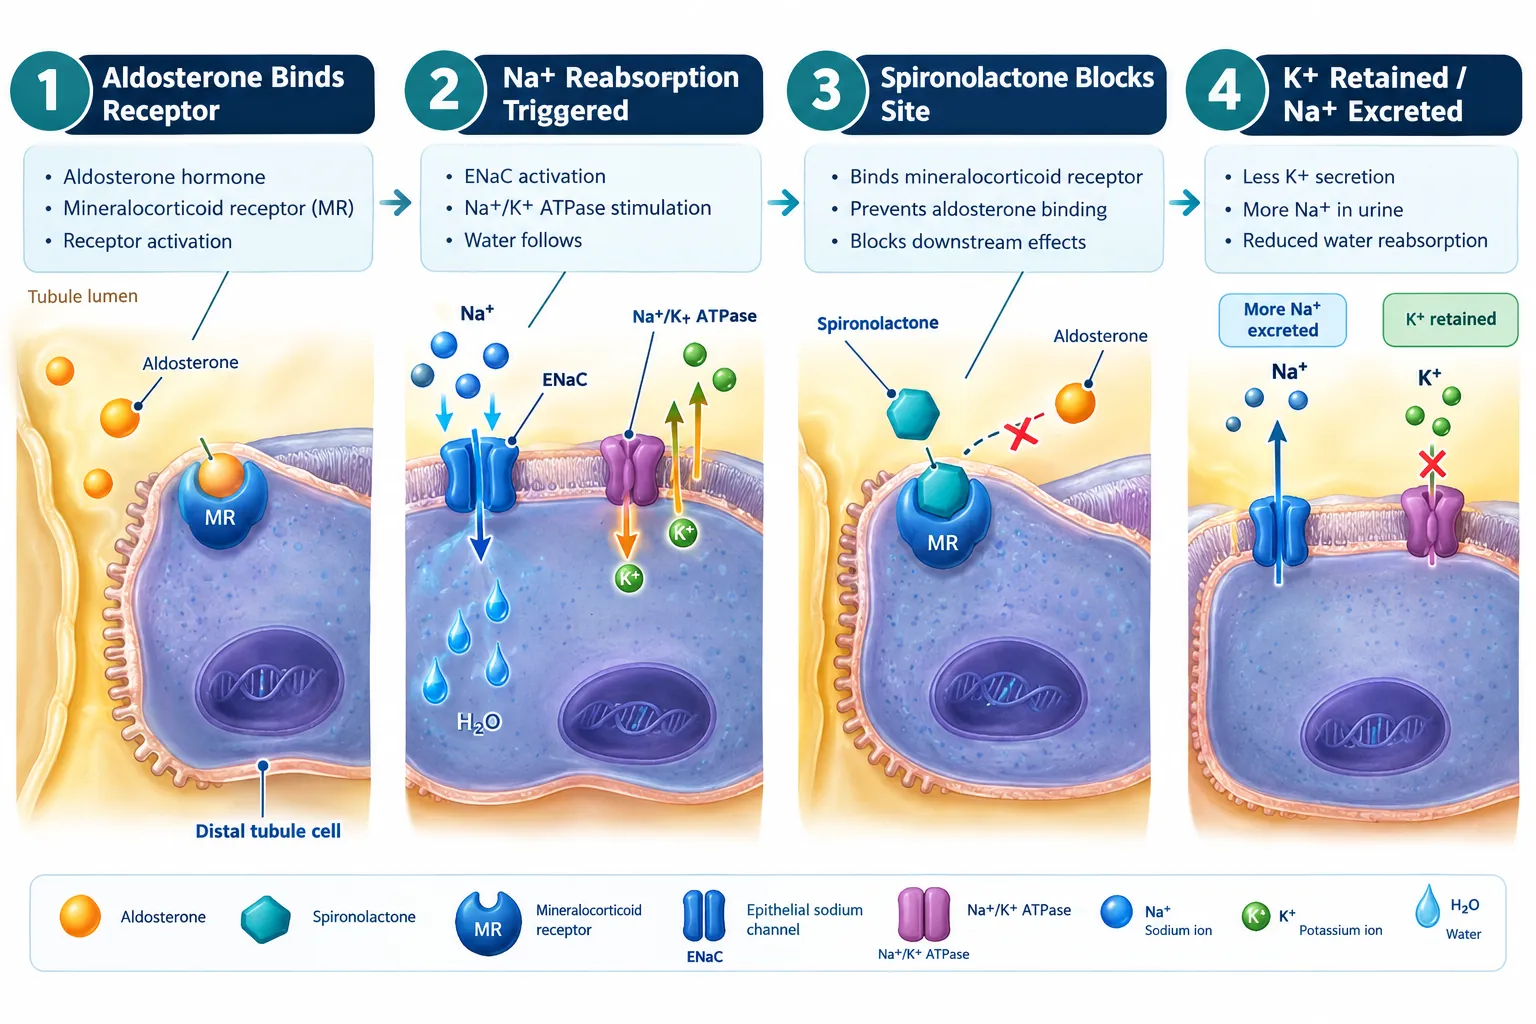
For researchers working with peptide models, this baseline pharmacology matters for three reasons:
- Fluid volume decreases predictably, which affects peptide distribution and concentration in biological fluids.
- Potassium retention alters the electrochemical environment of cells, potentially influencing receptor-ligand interactions.
- Aldosterone suppression disrupts the renin-angiotensin-aldosterone system (RAAS), creating secondary hormonal shifts that can confound peptide readouts.
Hyperaldosteronism, a state of excess aldosterone driving sodium retention and potassium wasting, remains one of the primary endocrine indications for spironolactone. In research models mimicking this condition, baseline aldosterone levels must be documented before interpreting any downstream peptide or hormonal data.
Researchers studying mitochondria-targeted compounds such as SS-31 peptide should note that cellular potassium gradients, altered by spironolactone's mechanism, can influence mitochondrial membrane potential measurements.
Potassium, Fluid Volume, and Electrolyte Readouts in Peptide Experiments
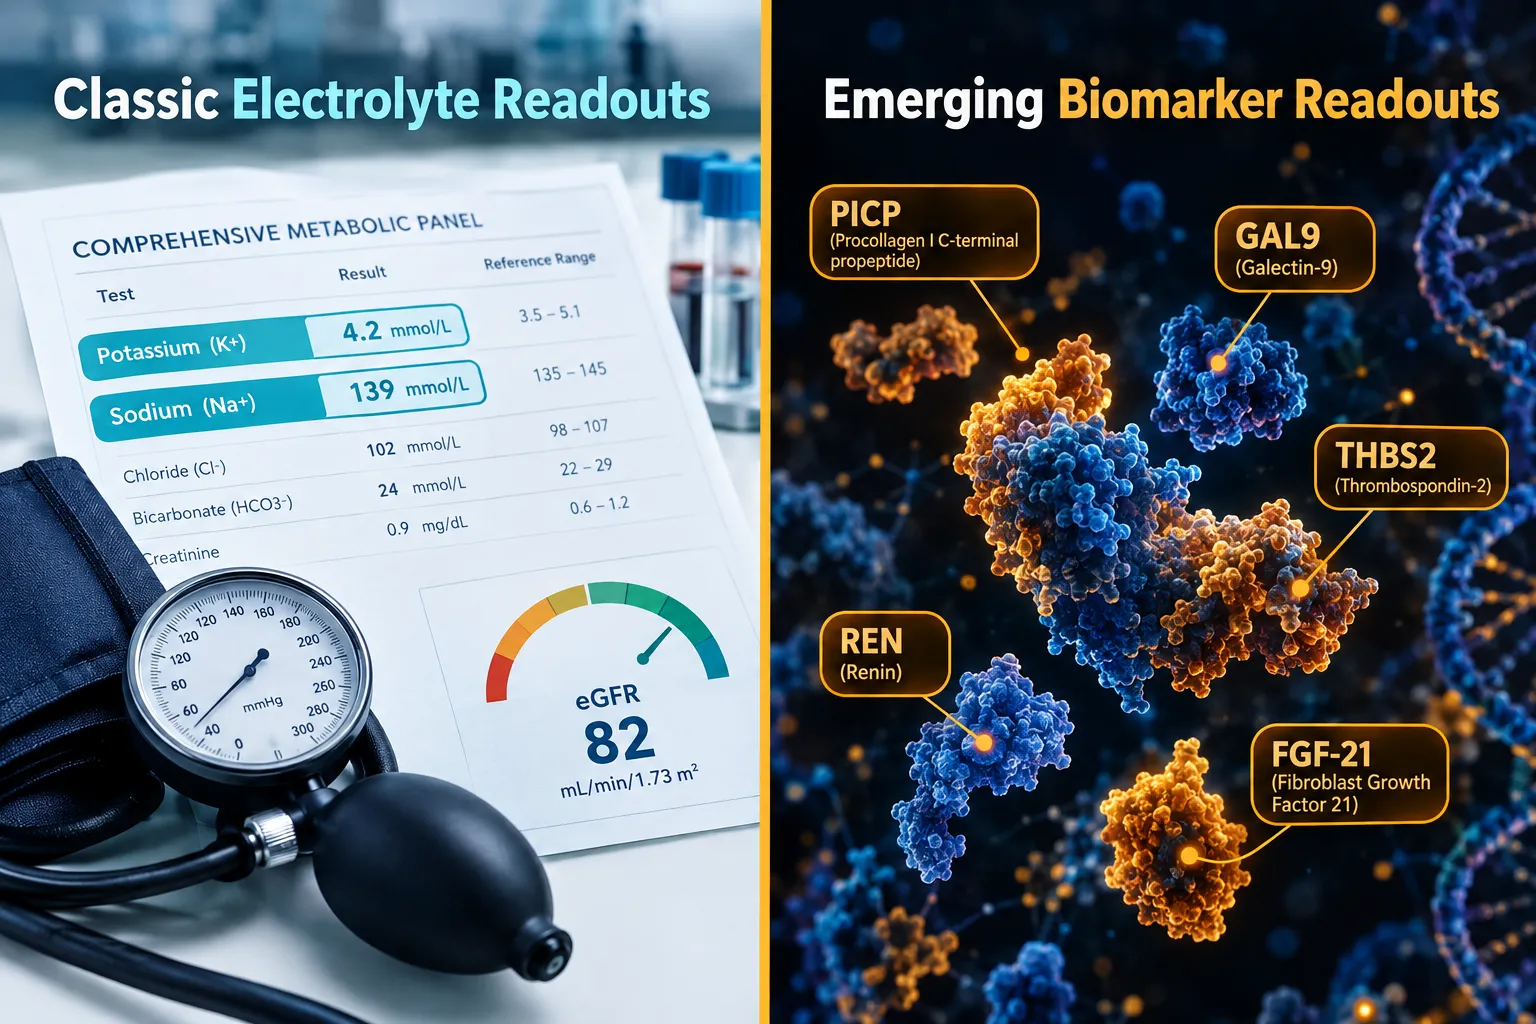
Because spironolactone is classified as a potassium-sparing diuretic, potassium monitoring is non-negotiable in any study protocol. Current NHS Specialist Pharmacy Service guidance updated in 2026 recommends potassium checks after one week of initiation, then monthly for three months, then at reduced frequency once values stabilize. A potassium level exceeding 6 mmol/L triggers a stop/seek-advice threshold, a figure that serves as a practical upper boundary in research safety monitoring as well.
Fluid volume changes are equally measurable and clinically meaningful. Spironolactone's natriuretic and diuretic effects reduce edema in heart failure, cirrhosis, and kidney disease models. In peptide metabolism studies, this volume reduction has direct consequences:
| Parameter | Expected Direction | Research Implication |
|---|---|---|
| Serum sodium | Decrease | Affects peptide solubility and distribution |
| Serum potassium | Increase | Alters membrane electrochemistry |
| Body weight | Decrease | Reflects fluid loss, not tissue change |
| Blood pressure | Decrease | Confounds cardiovascular peptide endpoints |
A 2026 NIH-hosted analysis in heart-failure-risk subjects found that after one month of spironolactone treatment, weight, serum sodium, and blood pressure all decreased, consistent with natriuresis and diuresis. These variables must be controlled or co-reported when interpreting peptide concentration data.
For studies involving GLP-1 peptides or metabolic signaling agents, fluid volume shifts can directly alter the apparent pharmacokinetics of co-administered peptides, making careful baseline fluid assessment essential.
Hormonal Readouts Beyond Electrolytes: What 2026 Studies Reveal
The most significant methodological development in spironolactone and peptide metabolism studies: aldosterone, potassium, fluid volume, and hormonal readouts is the growing recognition that spironolactone's effects extend into proteomic and hormonal territory far beyond simple electrolyte management.
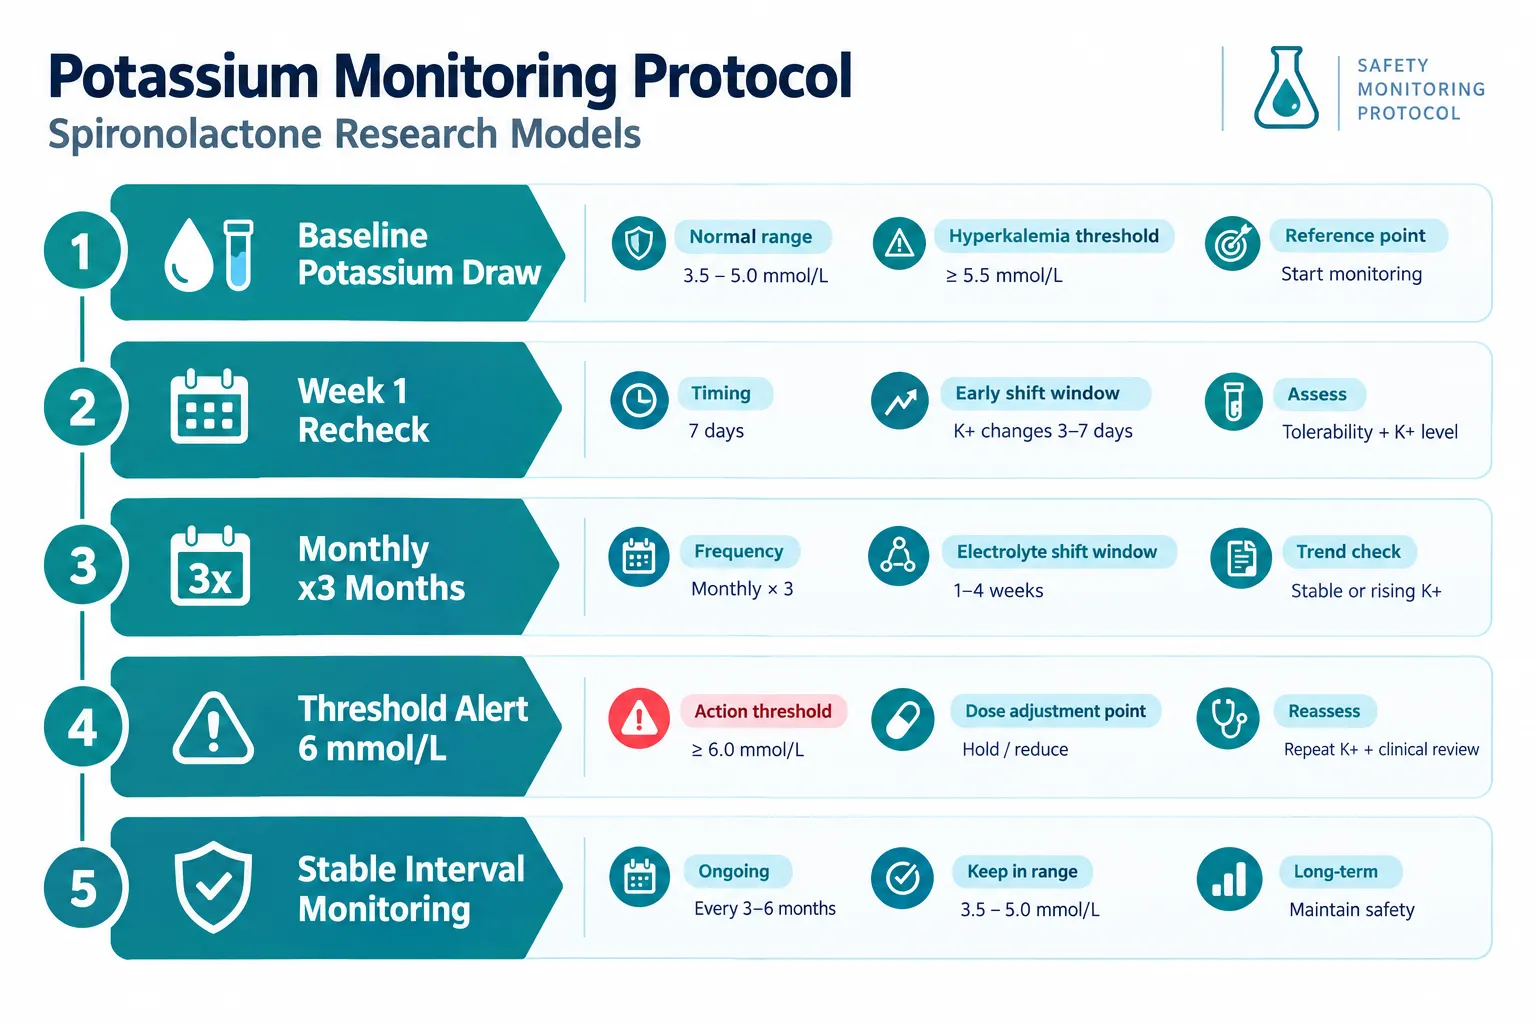
A 2026 NIH-published analysis in heart-failure-risk patients found that spironolactone reduced serum procollagen Type I C-terminal propeptide (PICP), a marker of cardiac fibrosis. Critically, the analysis implicated mediators including GAL9, THBS2, and REN, none of which are classic electrolyte markers. Changes in blood pressure, sodium, potassium, or eGFR were not the strongest variables associated with PICP shifts. This means that some hormonal and biomarker readouts in peptide studies are only partly explained by the drug's diuretic mechanism.
"Hormonal readouts in spironolactone-treated models reflect RAAS modulation at multiple levels, not just the aldosterone-potassium axis."
Separately, a 2026 veterinary proteomic study using combined angiotensin and spironolactone treatment reported changes in FGF-21, a metabolic signaling protein, pointing to downstream metabolic readouts tied to RAAS modulation. Researchers using lab-tested peptides in RAAS-modulated models should account for these off-target hormonal signals when designing assay panels.
For studies incorporating GLP-3 peptide formulations or other metabolic peptides, the FGF-21 signal is particularly relevant because it intersects with energy metabolism pathways that spironolactone indirectly modulates through RAAS suppression.
Researchers should also consider the SS-31 peptide benefits in oxidative stress contexts, since potassium retention and altered mitochondrial membrane potential may interact with mitochondria-targeted peptide activity in co-treatment models.
Three practical rules for interpreting hormonal readouts:
- Always separate electrolyte-driven changes from RAAS-mediated proteomic changes in your analysis plan.
- Include PICP, GAL9, or REN measurements if cardiac or fibrotic endpoints are relevant to your peptide model.
- Report fluid volume and weight changes alongside hormonal data to allow readers to distinguish diuretic from endocrine effects.
Conclusion
Designing rigorous spironolactone and peptide metabolism studies: aldosterone, potassium, fluid volume, and hormonal readouts requires more than tracking potassium levels. The 2026 research landscape makes clear that spironolactone modulates a layered hormonal environment, one where PICP, GAL9, THBS2, REN, and FGF-21 can shift independently of classic electrolyte markers.
Actionable next steps for researchers:
- Establish potassium and sodium baselines before any spironolactone co-treatment protocol.
- Apply the 6 mmol/L potassium threshold as a safety ceiling in preclinical models where applicable.
- Expand hormonal assay panels beyond electrolytes to include RAAS-related biomarkers.
- Control for fluid volume and weight changes when reporting peptide pharmacokinetic data.
- Review the latest SS-31 10mg research peptide considerations when designing mitochondria-targeted co-treatment studies with mineralocorticoid antagonists.
Understanding the full scope of spironolactone's hormonal footprint is no longer optional for peptide researchers, it is a prerequisite for producing interpretable, reproducible results.