

How to Read Metabolic Research Endpoints: A Practical Guide to A1C, LDL, Triglycerides, Waist Circumference, and hsCRP
Fewer than 20% of statin-treated patients with controlled LDL-C are actually free of residual cardiovascular risk, a gap that becomes visible only when researchers look beyond a single biomarker. This practical guide to reading metabolic research endpoints covers exactly that: how to interpret A1C, LDL, triglycerides, waist circumference, and hsCRP together, especially when evaluating studies on GLP-class peptides, MOTS-c analogs, and NNMT-related compounds where endpoint selection and baseline adjustment determine whether a result is meaningful or misleading.
Key Takeaways
- No single metabolic endpoint tells the full story; A1C, LDL, triglycerides, waist circumference, and hsCRP each capture a distinct mechanism.
- A1C targets in 2026 are stratified by hypoglycemia risk, age, and frailty, a numeric value must be read in that clinical context.
- LDL-C interpretation depends entirely on the patient's cardiovascular risk tier; the same number can signal success or undertreatment.
- hsCRP is now recognized as an independent predictor of cardiovascular events and should not be treated as a secondary or optional endpoint.
- Waist circumference anchors biochemical endpoints to visceral adiposity and insulin resistance, making it a critical companion measure.
Understanding the Five Core Endpoints
A solid reading of metabolic research endpoints starts with knowing what each marker actually measures, and what it misses.
A1C (Glycated Hemoglobin)
A1C reflects average blood glucose over roughly three months. Current 2026 guidance from major diabetes organizations sets stratified targets rather than a single universal number. For most adults with type 2 diabetes at low hypoglycemia risk, an A1C of 6.5% or below is considered optimal. For frail elderly individuals, those with dementia, or those with recurrent severe hypoglycemia, a range of 7.1-8.5% is considered reasonable. In pediatric studies, a target below 7% applies to most children, with 6.5% achievable in low-risk youth with type 2 diabetes.
Critically, A1C alone is no longer sufficient in modern trials. Continuous glucose monitoring metrics, particularly time in range above 70%, must accompany A1C to confirm that a lower value was achieved safely rather than through excess hypoglycemia. When reviewing GLP-class compound studies, always ask: was the A1C reduction accompanied by improved time-in-range data?
LDL Cholesterol
LDL-C thresholds are tiered by cardiovascular risk category. For low-risk individuals, a value below 116 mg/dL is acceptable. Moderate-risk patients target below 100 mg/dL. High-risk patients aim for below 70 mg/dL, and very-high-risk patients, such as those post-acute coronary syndrome, target below 55 mg/dL. In individuals with recurrent ASCVD events, targets can fall below 40 mg/dL, with evidence showing continued benefit at even lower levels without identified safety concerns.
This tiered structure means a trial reporting an LDL-C of 68 mg/dL could represent excellent control in a moderate-risk primary prevention cohort but inadequate control in a secondary prevention population. Endpoint interpretation must always reference the appropriate risk category, not an absolute number in isolation.
Triglycerides
Triglycerides are increasingly recognized as contributors to residual cardiovascular risk, particularly in patients whose LDL-C is already at target. A normal fasting triglyceride level sits below 150 mg/dL, with values above 200 mg/dL considered high and above 500 mg/dL posing a risk for pancreatitis. Current guidelines remain LDL-centric, but accumulating evidence implicates elevated triglycerides and remnant lipoproteins as independent risk factors. Upcoming guideline revisions are expected to formalize more explicit triglyceride-based goals. In studies of compounds like retatrutide endpoints or GLP-3 peptides, triglyceride data should be treated as a leading indicator of future threshold shifts, not a secondary footnote.
Waist Circumference
Waist circumference is a practical proxy for visceral adiposity and insulin resistance. Standard thresholds flag elevated risk at above 88 cm in women and above 102 cm in men, though ethnicity-adjusted values are increasingly used. In cardiometabolic trials, waist circumference anchors biochemical endpoints to actual body composition. An improvement in A1C and LDL-C without a reduction in waist circumference may indicate partial but incomplete metabolic risk modification. Research on visceral fat outcomes consistently shows that central adiposity independently predicts insulin resistance, dyslipidemia, and cardiovascular events beyond what lipid panels capture alone.
hsCRP (High-Sensitivity C-Reactive Protein)
hsCRP is the most robust available biomarker of residual inflammatory cardiovascular risk. A value at or above 2 mg/L is now classified as a risk-enhancing factor in ASCVD prevention guidelines, and universal screening in both primary and secondary prevention is recommended as of 2026. Elevated hsCRP predicts major adverse cardiovascular events over decades of follow-up, and it remains strongly predictive of recurrent events even in statin-treated patients with normal LDL-C. In trials, a substantial fall in LDL-C without a corresponding reduction in hsCRP leaves significant vascular risk unaddressed.
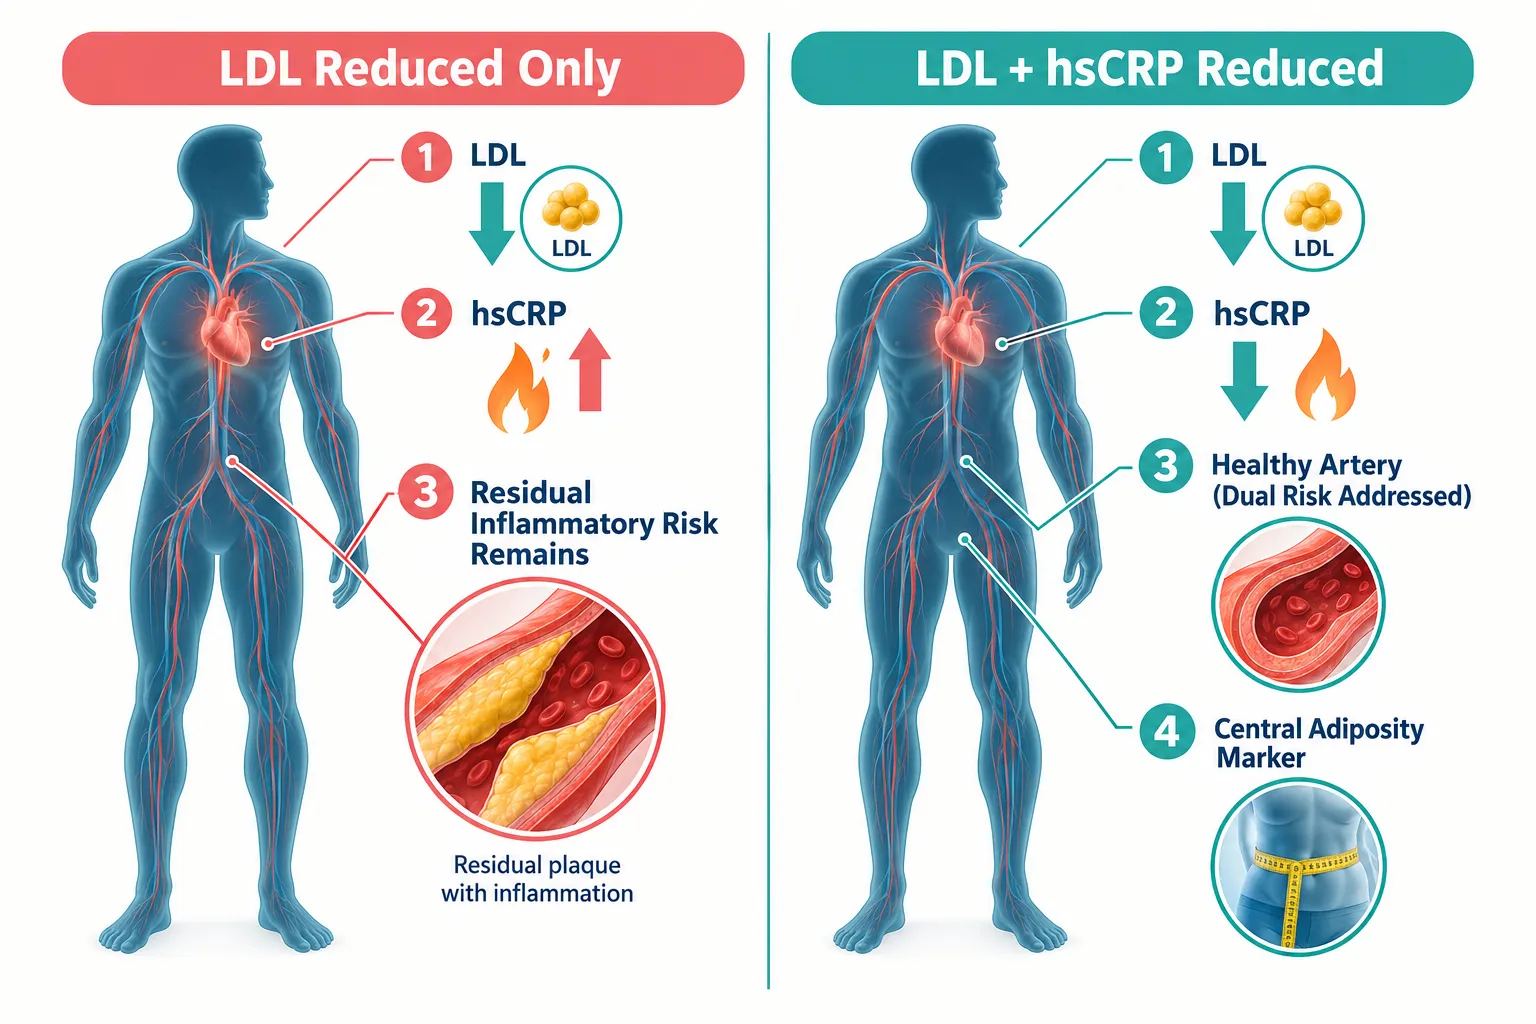
Why One Biomarker Cannot Stand In for a Complete Mechanism
The most common error in reading metabolic research is treating a single endpoint as a surrogate for the full cardiometabolic picture. This matters especially when evaluating compounds that operate through multiple pathways.
Consider a study on a GLP-class compound that reports a 1.2% reduction in A1C. That result is clinically meaningful, but it tells nothing about whether LDL-C moved, whether hsCRP fell, or whether waist circumference changed. A compound that lowers glucose while leaving visceral fat and systemic inflammation untouched has addressed only one of several interconnected mechanisms. For context on how polypeptide compounds differ from small-molecule drugs in their cardiometabolic effects, the analysis of tesofensine, GLP-3, retatrutide, and GLP-2-T illustrates why endpoint panels must match the mechanism being tested.
The same logic applies to MOTS-c research. MOTS-c is a mitochondria-derived peptide that influences insulin sensitivity and energy metabolism. A trial measuring only A1C misses the compound's potential effects on lipid oxidation, triglyceride clearance, and inflammatory signaling. Similarly, NNMT (nicotinamide N-methyltransferase) inhibition research, relevant to compounds like 5-amino-1MQ, targets metabolic reprogramming at the cellular level, where waist circumference and hsCRP may be more sensitive endpoints than A1C in short-duration studies.
Baseline adjustment is equally critical. A trial that does not stratify participants by baseline hsCRP, cardiovascular risk tier, or waist circumference cannot isolate the compound's effect from baseline population differences. A participant with an hsCRP of 0.5 mg/L at baseline has a fundamentally different inflammatory risk profile than one entering the study at 4 mg/L. Reporting a mean hsCRP change without this stratification obscures whether the compound meaningfully reduced inflammatory risk or simply reflected a low-inflammation cohort at the outset.
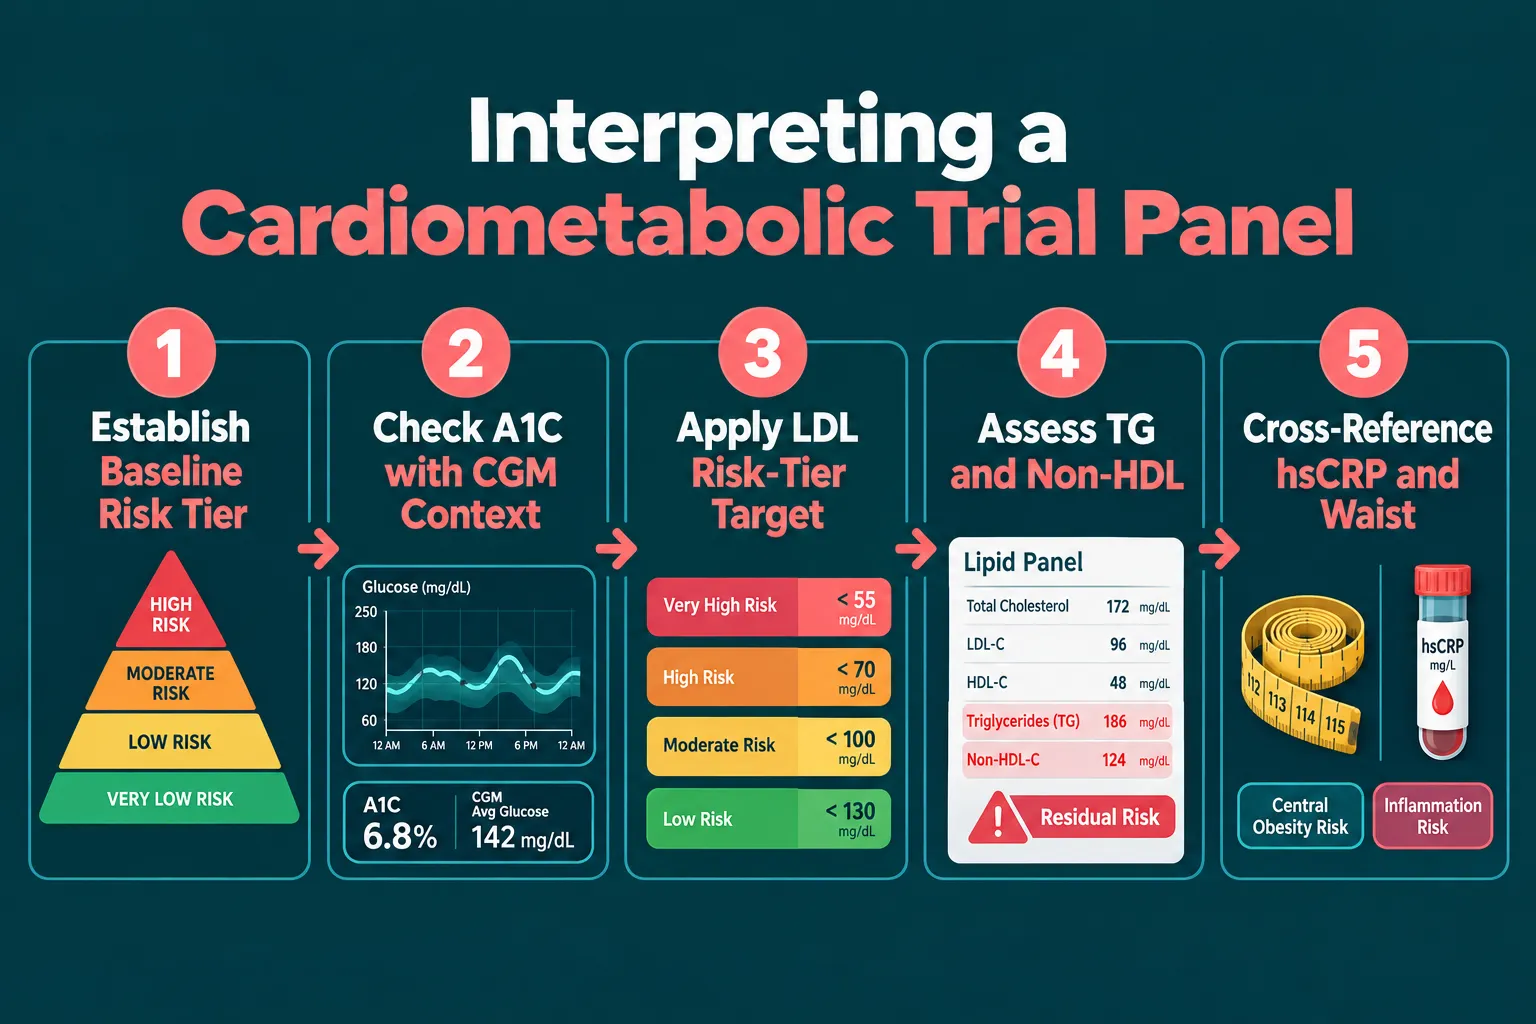
A Practical Framework for Reading Metabolic Research Endpoints
The following framework applies directly when reviewing trial data on cardiometabolic compounds, including those studied in the context of tesa benefits for visceral fat reduction or SS-31 elamipretide for mitochondrial and cardiometabolic function.
| Step | Action | Key Question |
|---|---|---|
| 1 | Establish baseline risk tier | What was the population's cardiovascular risk category at enrollment? |
| 2 | Contextualize A1C | Was the change accompanied by CGM time-in-range data? Was hypoglycemia tracked? |
| 3 | Apply LDL risk-tier target | Does the reported LDL-C meet the threshold appropriate for this cohort's risk level? |
| 4 | Assess triglycerides and non-HDL | Were remnant lipoproteins measured alongside LDL-C? |
| 5 | Cross-reference hsCRP and waist | Did inflammatory burden and central adiposity change in the same direction as biochemical endpoints? |
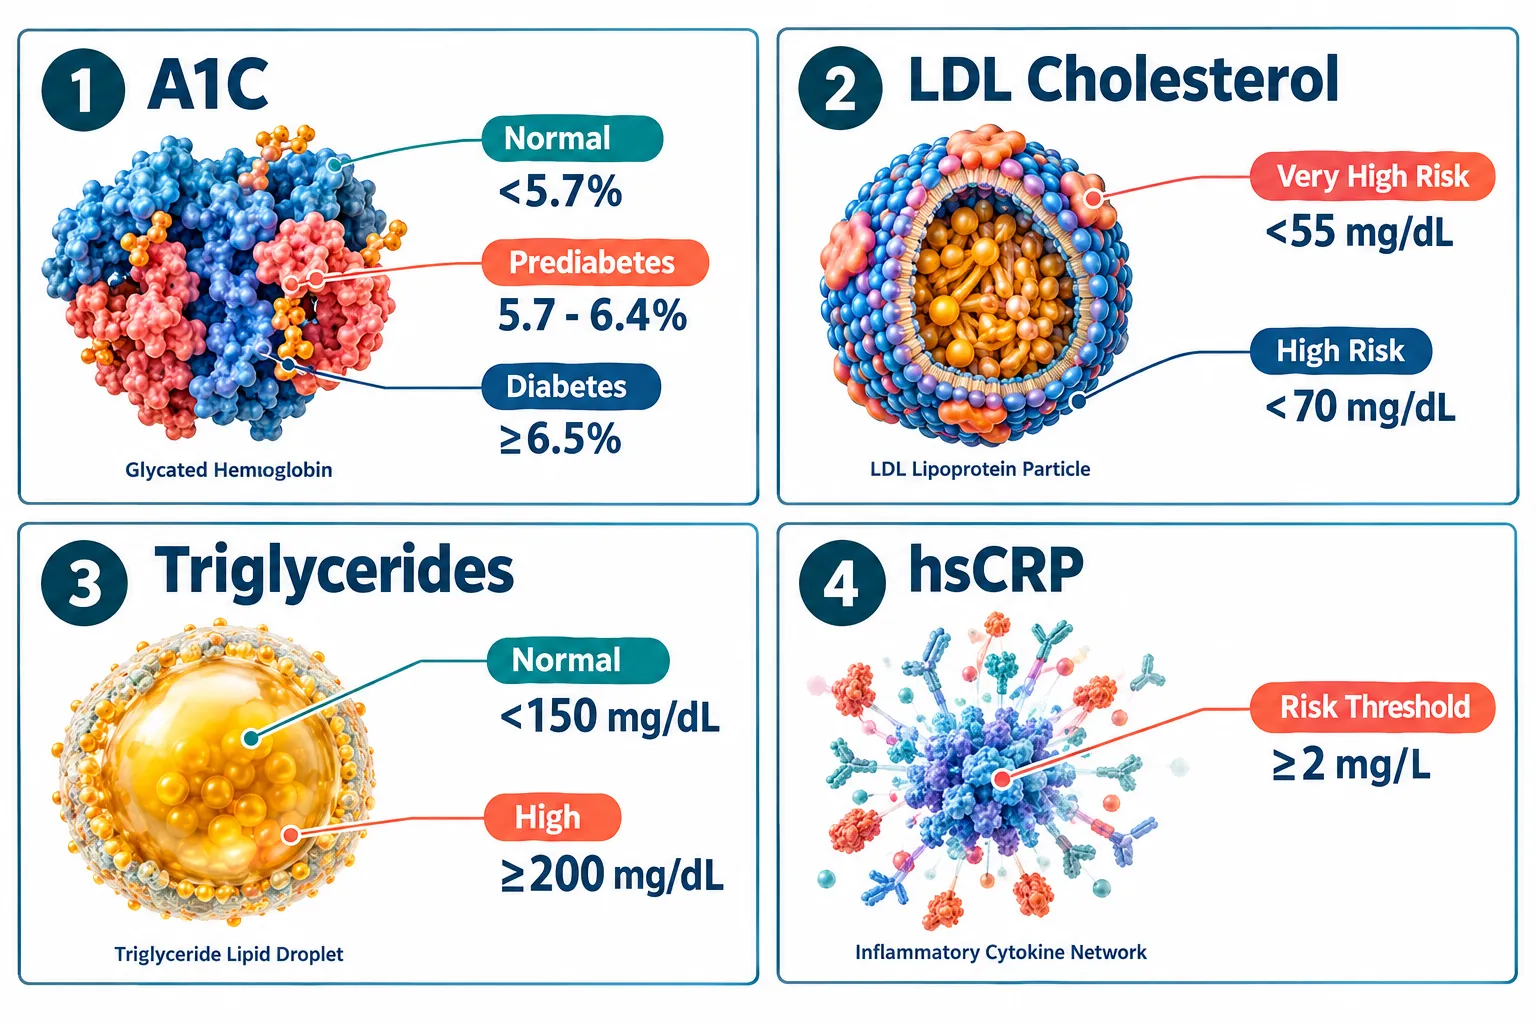
Reading the endpoints together reveals the mechanism. A compound that lowers A1C, reduces waist circumference, and decreases hsCRP is likely acting on insulin sensitivity, visceral fat, and systemic inflammation simultaneously, a genuinely comprehensive cardiometabolic effect. A compound that lowers only LDL-C may be addressing lipid transport without touching the inflammatory or adiposity components of risk.
Non-HDL cholesterol deserves mention here. Because it captures LDL plus remnant lipoproteins, non-HDL is a more complete lipid endpoint than LDL-C alone. In UK cardiovascular prevention audits, non-HDL targets of 2.6 mmol/L or below are used alongside LDL targets to judge treatment adequacy. Trials that report only LDL-C without non-HDL leave the remnant lipoprotein contribution to risk unaccounted for.
Conclusion
Reading metabolic research endpoints accurately requires treating A1C, LDL, triglycerides, waist circumference, and hsCRP as a complementary panel rather than interchangeable alternatives. Each marker captures a distinct biological mechanism, and no single value substitutes for the full picture.
Actionable next steps for researchers and informed readers:
- When reviewing a trial, check whether the endpoint panel matches the compound's proposed mechanism of action.
- Confirm that A1C results are accompanied by CGM-derived time-in-range data and hypoglycemia rates.
- Identify the study population's cardiovascular risk tier before judging whether an LDL-C value represents success or residual undertreatment.
- Treat hsCRP as a primary endpoint in any study involving inflammatory pathways, not a supplementary add-on.
- Flag any trial that reports improvements in biochemical markers without measuring waist circumference, central adiposity may be the missing variable explaining why risk did not fully resolve.
The field is moving toward multi-endpoint cardiometabolic panels as the standard for evaluating both pharmaceutical and peptide-based interventions. Understanding how to read those panels is the foundational skill for interpreting the next generation of metabolic research.