

Omeprazole, Famotidine, and GLP-2-T Research: Controlling Gastric-Acid Variables in Intestinal Models
Gastric acid suppression is one of the most frequently overlooked confounders in intestinal peptide research, yet pH shifts as small as one unit can alter epithelial permeability, reshape the luminal microbiome, and mask or amplify the very signals a study is designed to measure. When the research involves a novel compound like GLP-2-T alongside established acid modulators, the stakes for rigorous variable control become even higher. This article examines how omeprazole, famotidine, and GLP-2-T research intersects in the context of controlling gastric-acid variables in intestinal models, and what investigators must document to produce reproducible, interpretable data.
Key Takeaways
- Omeprazole (PPI) and famotidine (H2RA) suppress gastric acid through distinct mechanisms, producing different pH profiles, microbiome effects, and experimental confounders.
- Acid suppression alone can accelerate mucosal repair, meaning it must be treated as an active variable, not a neutral background condition, in intestinal models.
- GLP-2-T is positioned as a downstream effector of mucosal physiology; its readouts are directly influenced by the acid environment established before or during exposure.
- Combination "pH clamp" regimens using both drug classes can stabilize luminal pH rapidly, but they introduce additive microbiome disruption that requires dedicated endpoint tracking.
- Endpoint selection, particularly tight-junction integrity, transepithelial resistance, and microbial diversity indices, must be pre-specified with acid exposure conditions fully recorded.
Why Acid Suppression Becomes a Study Confounder
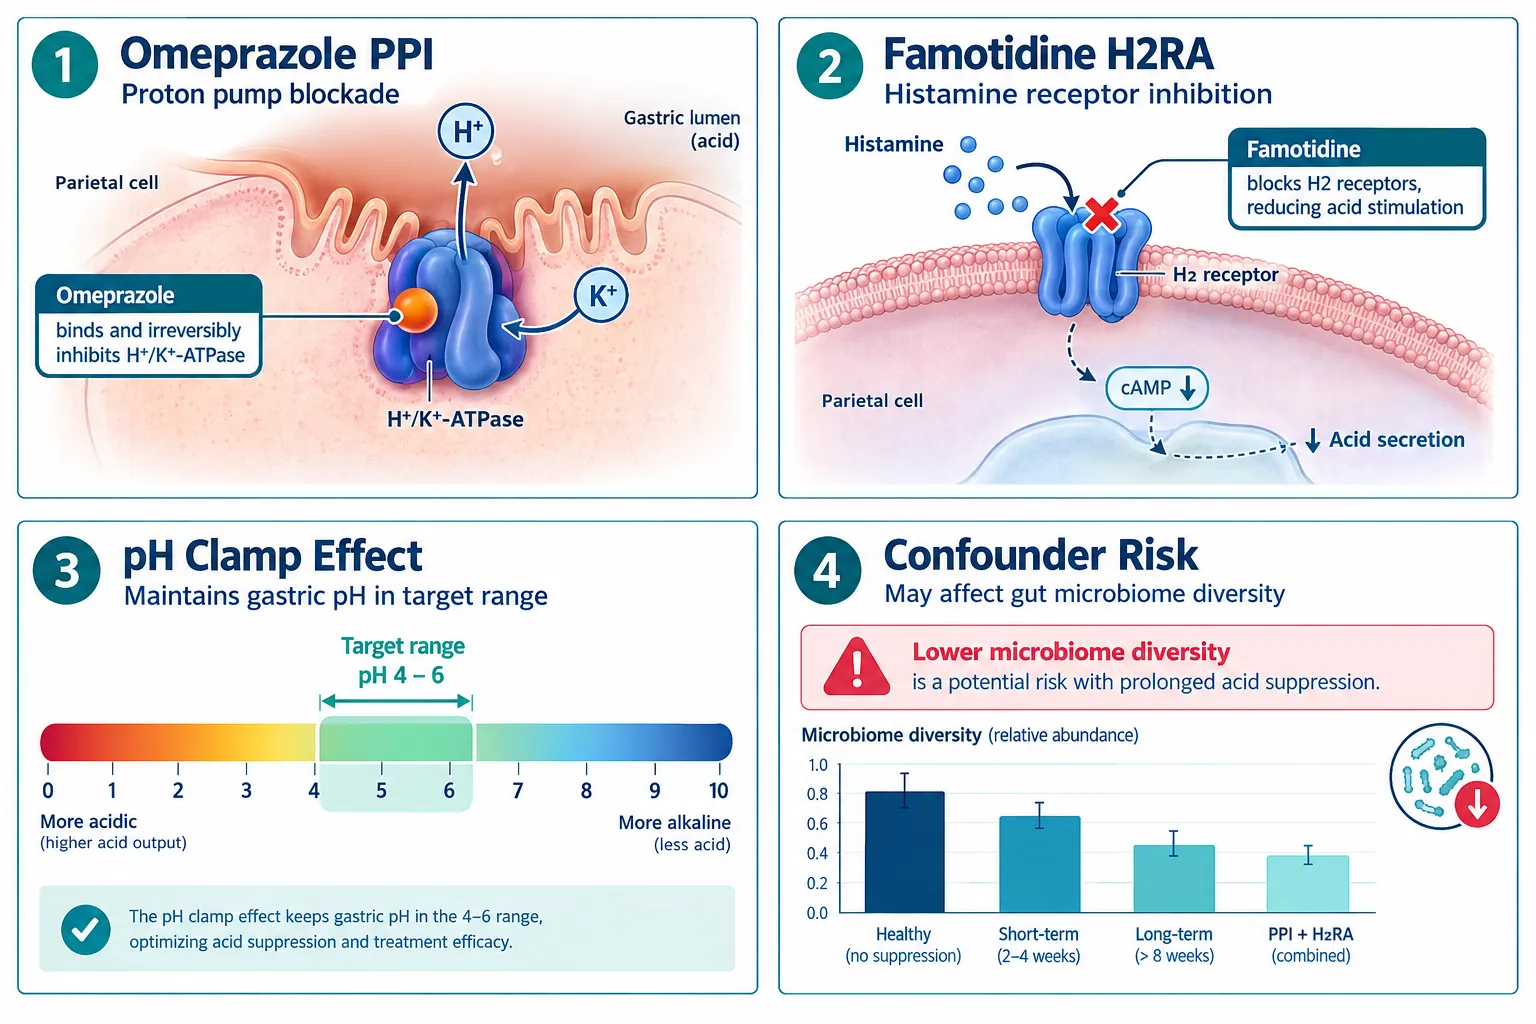
Omeprazole is a proton pump inhibitor (PPI). It irreversibly blocks the H+/K+-ATPase enzyme on gastric parietal cells, producing sustained acid suppression that persists well beyond the compound's plasma half-life. Famotidine is an H2 receptor antagonist (H2RA). It competes with histamine at the H2 receptor, producing faster but more transient pH elevation. These two mechanisms matter enormously for experimental design because they create different temporal pH profiles inside any intestinal model system.
Key pharmacodynamic differences:
| Feature | Omeprazole (PPI) | Famotidine (H2RA) |
|---|---|---|
| Onset of action | 1-4 hours | 30-60 minutes |
| Duration of effect | 24-72 hours | 6-12 hours |
| pH ceiling | Higher, more sustained | Moderate, variable |
| Microbiome impact | Greater oral-to-gut bacterial shift | Lower, more localized |
| Reversibility | Irreversible (enzyme turnover needed) | Reversible, competitive |
When either agent is present in a model without being explicitly recorded as an independent variable, it can independently accelerate gastric wound repair, alter tight-junction protein expression, and change luminal bacterial composition. Research using stress-ulcer and mucosal-injury models has confirmed that acid suppression is a dominant variable, not a passive background condition.
"Acid suppression is not a neutral scaffold. It is an active intervention that reshapes the biological terrain on which every other compound must act."
For investigators exploring GLP peptides for research purposes, this means the acid environment must be treated with the same rigor as the peptide dose itself.
GLP-2-T in Intestinal Models: Where Acid Control Intersects
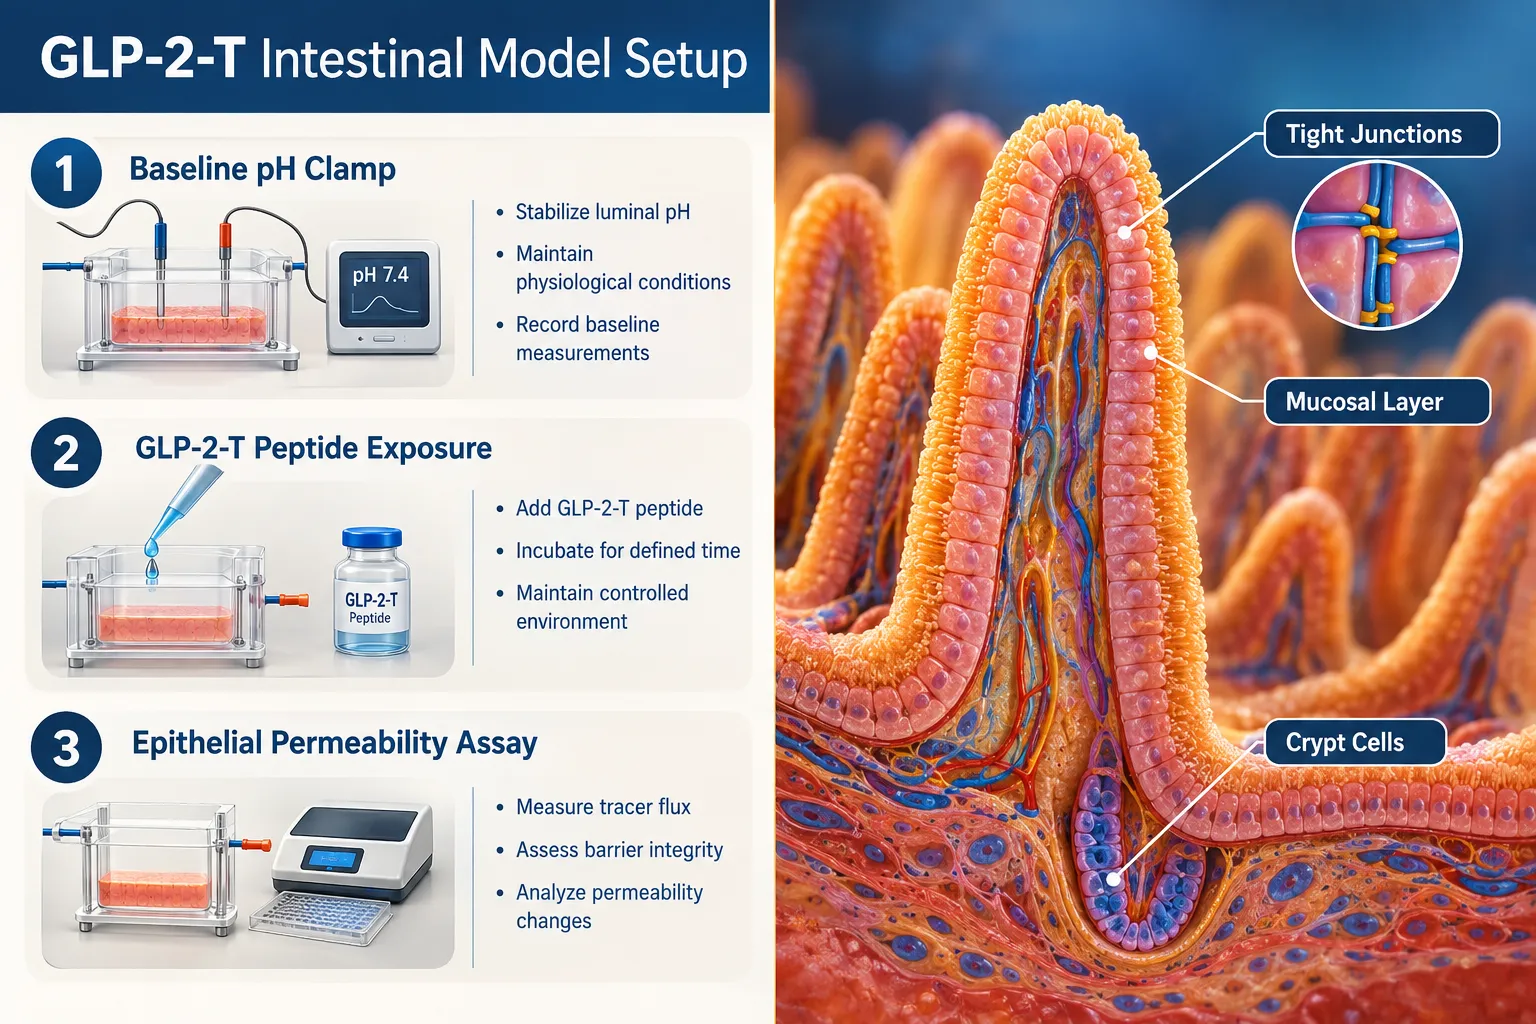
GLP-2 (glucagon-like peptide-2) is a 33-amino-acid hormone secreted by intestinal L-cells. Its primary roles include promoting mucosal growth, reducing intestinal permeability, and modulating gastric acid secretion itself, making it uniquely entangled with the acid variables described above. Clinical GLP-2 analogs such as teduglutide have established this peptide class as a benchmark for intestinal trophic research.
GLP-2-T refers to a research-stage analog designed to engage GLP-2 receptors with modified pharmacokinetics or receptor selectivity. Because GLP-2-T is predicted to act downstream of the acid environment, the luminal pH at the time of peptide exposure directly conditions the model's response. Specifically:
- Epithelial permeability endpoints (transepithelial electrical resistance, FITC-dextran flux) are sensitive to baseline pH; an uncontrolled acid shift can mimic or cancel GLP-2-T's barrier-tightening effects.
- Mucosal proliferation markers (crypt cell mitosis, villus height) respond to both acid suppression and GLP-2R activation, creating overlapping signal if both variables are active simultaneously.
- Microbiome diversity indices are altered by PPIs more profoundly than H2RAs; since GLP-2-T research often includes microbiome endpoints, the choice between omeprazole and famotidine is not interchangeable.
For context on related peptide mechanisms, the comparison of LL-37 versus SS-31 peptide benefits illustrates how overlapping biological targets demand careful endpoint separation, a principle that applies directly here.
Researchers exploring GLP-3 Reta compounds will recognize that the same acid-variable logic governs any GLP-family peptide study conducted in an intestinal model system.
Experimental Workflow: Recording and Controlling Acid Variables

Controlling gastric-acid variables in intestinal models requires a structured approach to both pre-treatment conditions and endpoint documentation. The following workflow reflects current preclinical best practice when coupling acid suppression with GLP-2 or GLP-2-T exposure.
Step-by-step acid control protocol:
- Define the pH target range before any peptide is introduced. Most intestinal epithelial models require a luminal pH between 4.5 and 6.5 for physiologically relevant responses.
- Select the acid suppressor based on study duration. Use famotidine for short-window experiments (under 12 hours) where reversibility is needed. Use omeprazole for sustained pH clamping over multi-day models.
- Consider combination regimens cautiously. Omeprazole-plus-famotidine combinations can achieve rapid, stable pH clamping, useful for acute injury models, but they amplify microbiome disruption and must be documented as a compound intervention, not a single variable.
- Record acid exposure as an independent variable in all statistical models. Do not treat it as a preprocessing step.
- Pre-specify microbiome endpoints separately from epithelial endpoints. PPI-driven oral-to-gut bacterial translocation can confound 16S rRNA diversity data if not controlled with a matched acid-suppression arm.
- Introduce GLP-2-T only after pH stabilization is confirmed. Introducing the peptide during an acid transient will produce unreliable permeability and proliferation data.
Endpoints requiring dedicated acid controls:
- Tight-junction protein expression (claudin-1, occludin, ZO-1)
- Transepithelial electrical resistance (TEER)
- Villus-to-crypt ratio
- Mucosal cytokine profiles (IL-6, TNF-alpha)
- Microbial alpha- and beta-diversity indices
For researchers interested in how mitochondrial peptides interact with similar tissue-integrity endpoints, the work on SS-31 mitochondrial research and wound healing models provides useful methodological parallels for endpoint separation strategies.
Choosing Between PPIs and H2RAs for GLP-2-T Studies
The choice is not merely pharmacological, it is experimental design. PPIs offer superior pH stability for multi-day intestinal organoid or ex-vivo tissue models, but their microbiome effects introduce a confounder that is difficult to isolate. H2RAs preserve a more physiological luminal bacterial environment at the cost of pH variability. Neither is universally superior; the correct choice depends on which endpoints are primary.
For GLP-1 Reta research contexts, where metabolic and mucosal endpoints often overlap, this trade-off is especially consequential and should be addressed explicitly in the methods section of any publication or report.
Conclusion
Omeprazole, famotidine, and GLP-2-T research demands that controlling gastric-acid variables in intestinal models be treated as a first-order experimental priority, not an afterthought. The core actionable steps are clear: select the acid suppressor that matches study duration and microbiome sensitivity requirements, document pH exposure as an independent variable in every statistical model, stabilize luminal pH before introducing GLP-2-T, and pre-specify epithelial permeability and microbiome endpoints with matched acid-control arms.
Investigators should also cross-reference their endpoint selection against established peptide research frameworks, including VEGF upregulation studies and wound healing compound models, where overlapping biological targets have required similar variable-isolation strategies. As GLP-2-T research matures in 2026, the quality of acid-variable documentation will likely become a primary criterion for peer review and reproducibility assessment.