Retatrutide 2026 Trial Data: Interpreting Triple-Agonist Results Across Obesity, Diabetes, and Cardiovascular-Risk Populations
Weight loss drugs have historically plateaued at 10-15% body weight reduction. Retatrutide 2026 trial data is shattering that ceiling, but the numbers only make sense when you know which population produced them.
As phase 3 results continue to accumulate under the TRIUMPH program, clinicians, researchers, and informed readers face a critical interpretive challenge. The same molecule can appear to perform very differently depending on baseline BMI, diabetes status, dose escalation schedule, and how long participants were followed. Understanding these variables is the key to reading retatrutide results accurately across obesity, diabetes, and cardiovascular-risk populations.
Key Takeaways
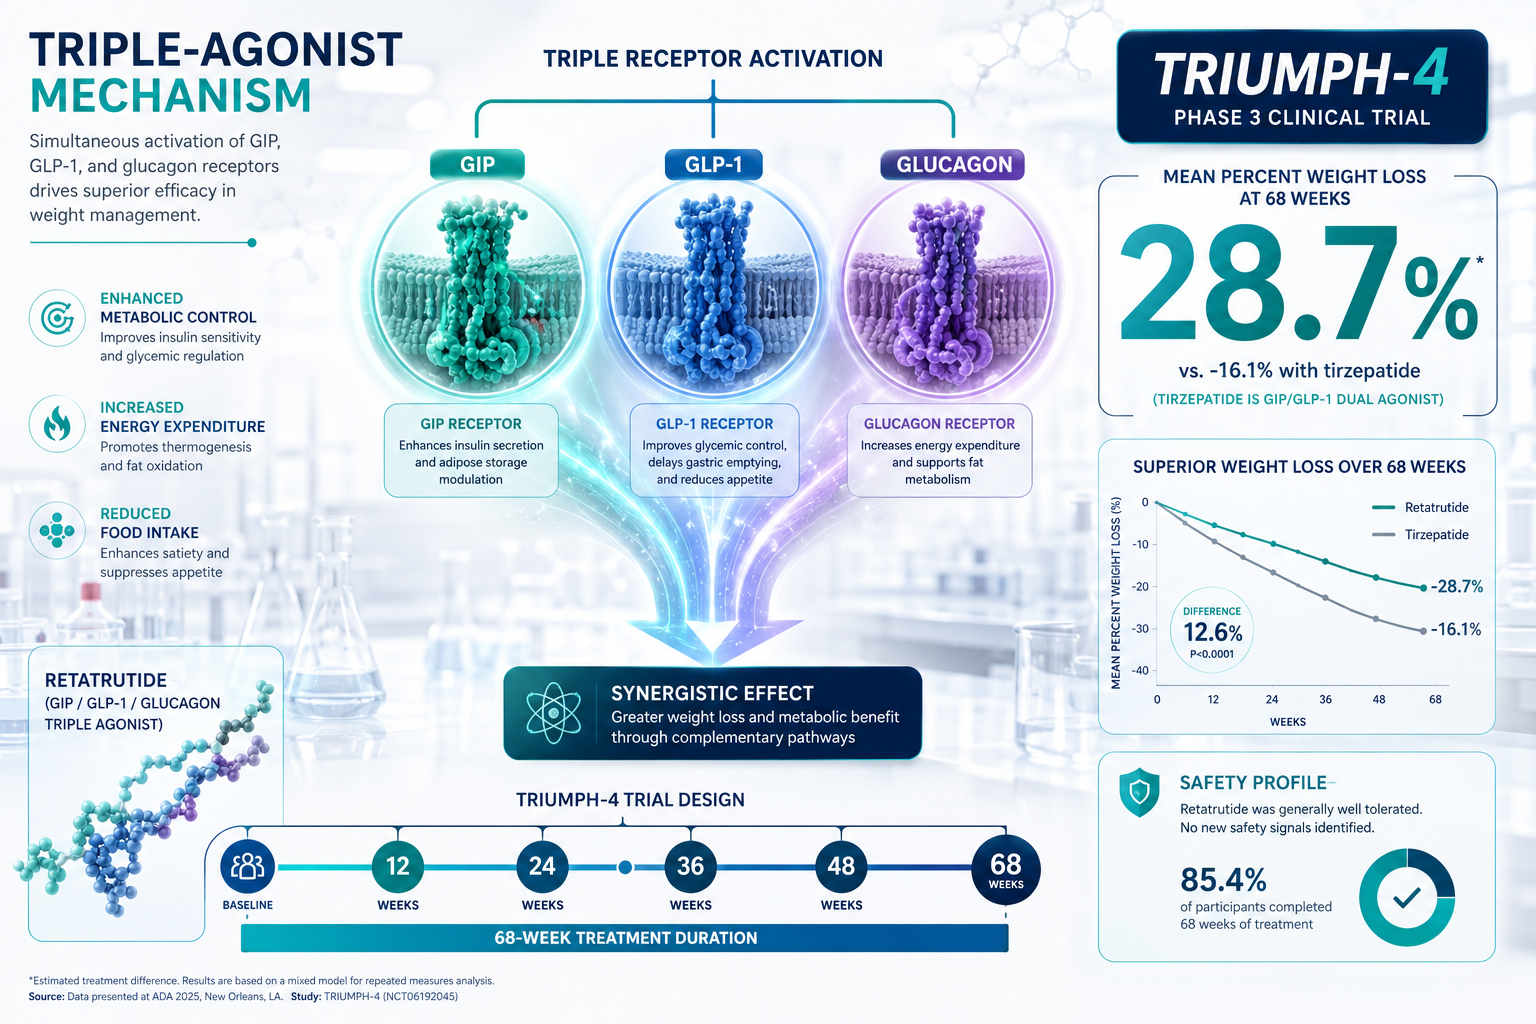
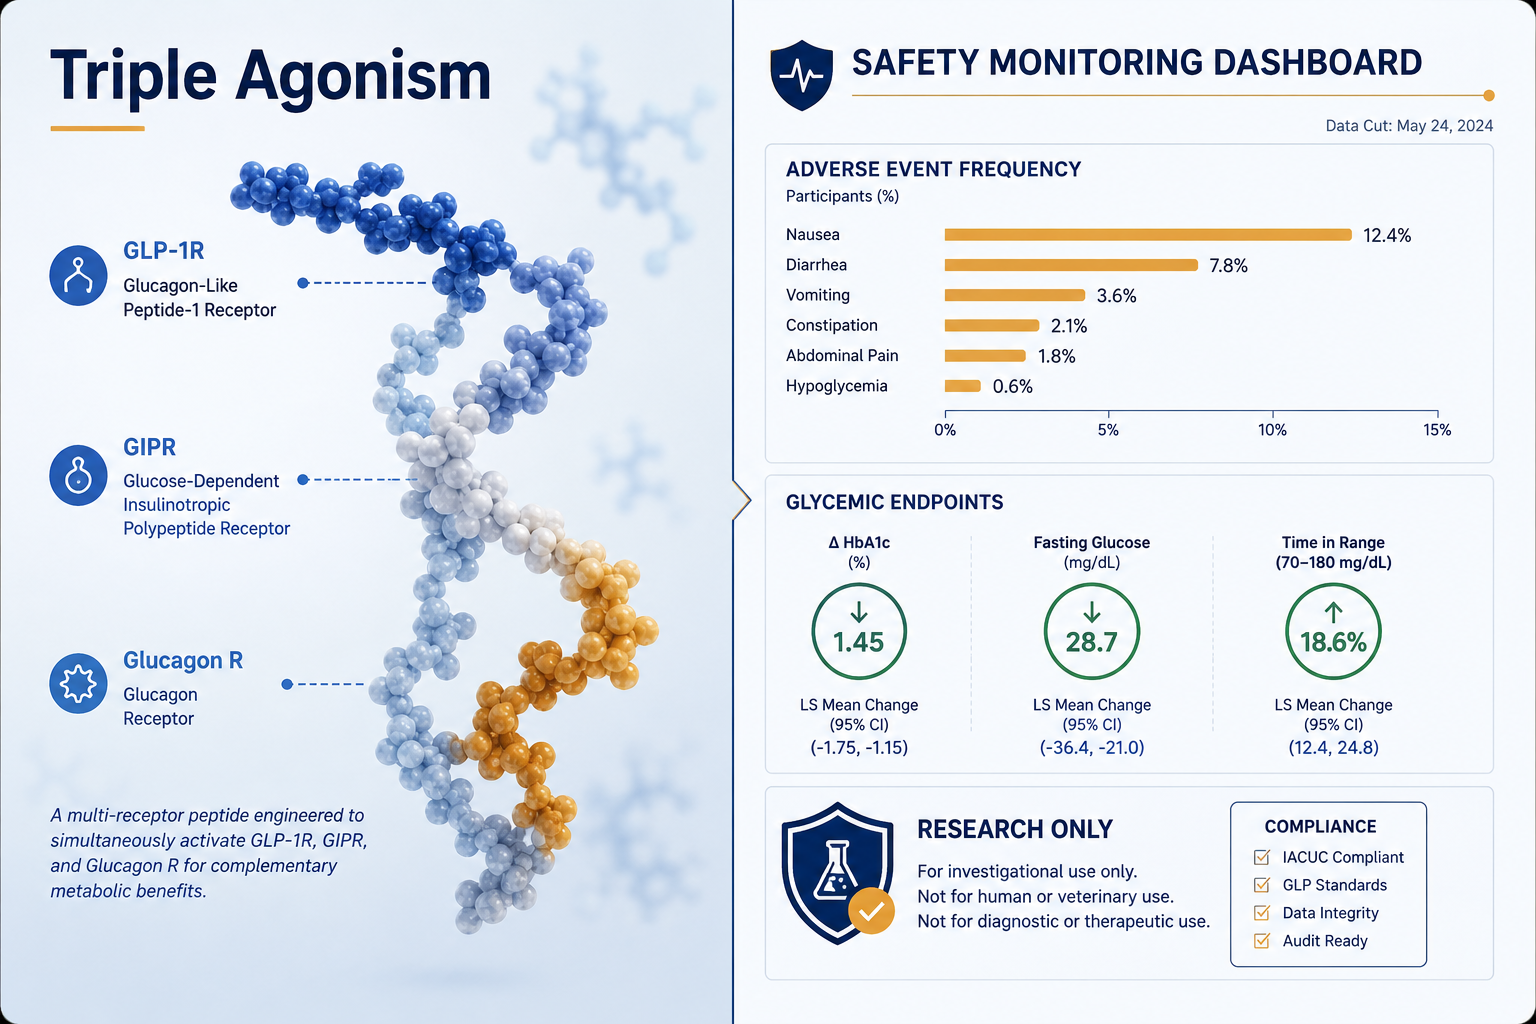
- Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, producing weight loss and metabolic effects beyond any single-agonist drug currently approved.
- The TRIUMPH-1 trial in adults with obesity but without diabetes reported unprecedented weight loss over 80 weeks, exceeding outcomes seen with semaglutide or tirzepatide in comparable trials.
- Results in people with type 2 diabetes are strong but modestly lower in absolute weight reduction, largely because diabetes biology blunts the full anorexigenic response.
- Cardiovascular outcomes data is still maturing as of late 2026; cardiometabolic risk factors improve, but hard endpoint confirmation is pending.
- Population selection, dose escalation, and follow-up duration are the three variables most likely to mislead readers who compare trial results without accounting for them.
How the Triple-Agonist Mechanism Changes the Baseline Interpretation
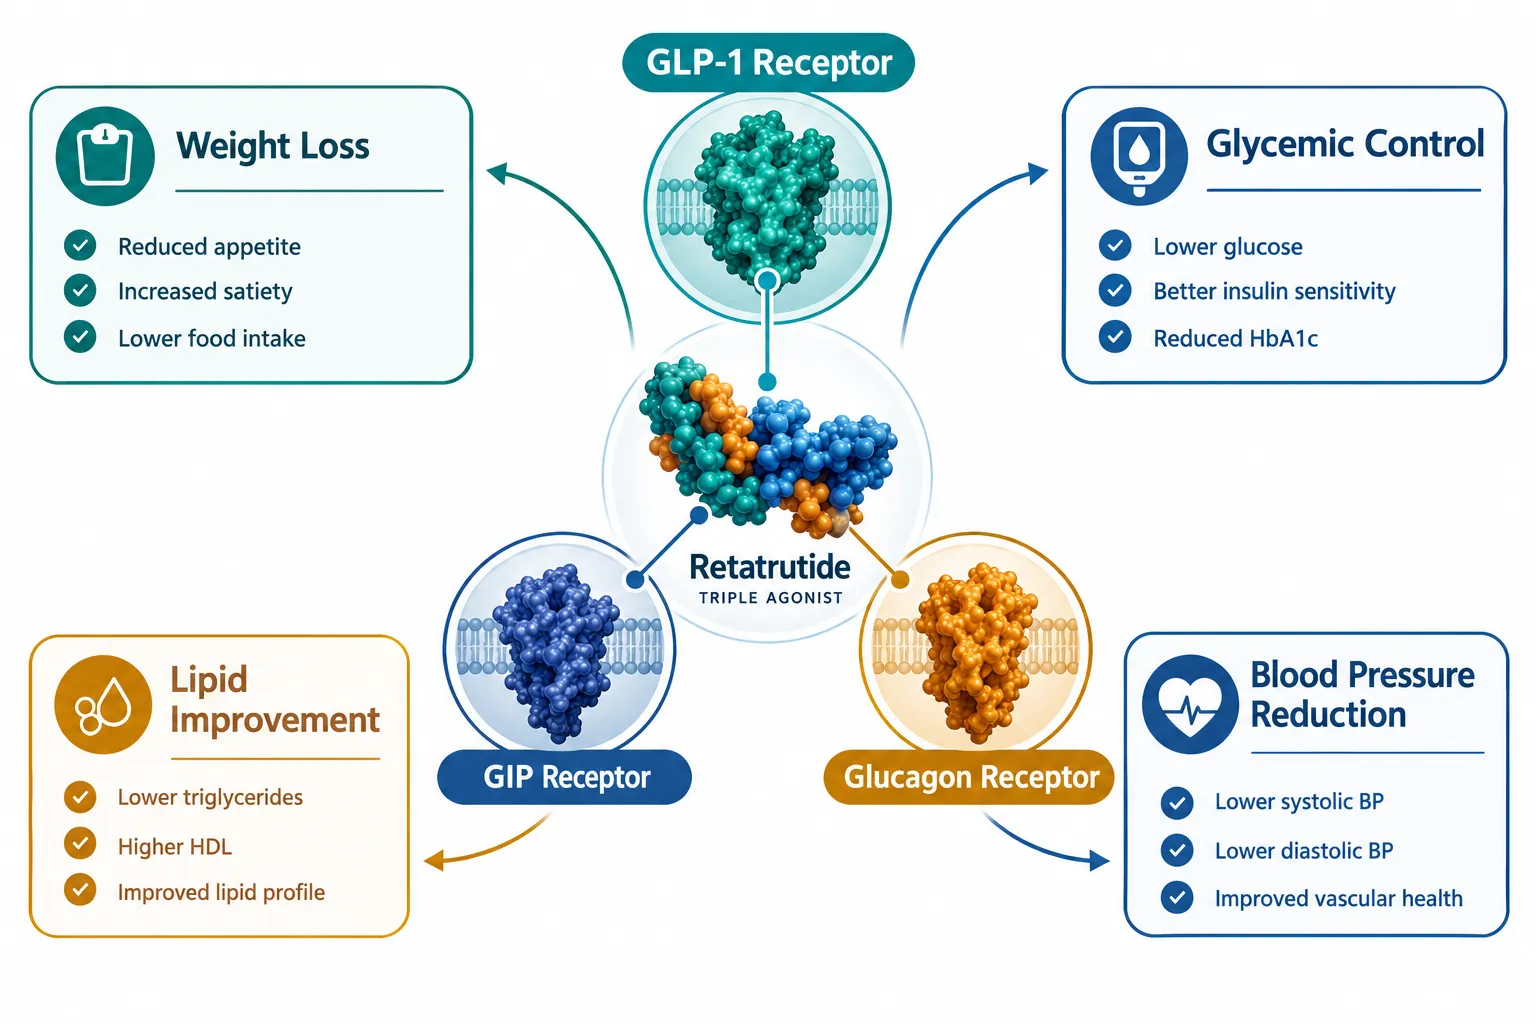
Most GLP-1 receptor agonists work through a single pathway. Tirzepatide added a second, GIP co-agonism, and generated headlines. Retatrutide adds a third: glucagon receptor activation. This matters enormously for interpretation because each receptor contributes differently depending on a patient's metabolic state.
GLP-1 activation suppresses appetite and slows gastric emptying. GIP co-agonism amplifies insulin secretion and may enhance GLP-1 sensitivity. Glucagon receptor activation drives energy expenditure and accelerates fat oxidation. In a person with severe obesity but normal glucose metabolism, all three pathways operate near full capacity. In a person with long-standing type 2 diabetes, GIP sensitivity is often diminished and glucagon dysregulation complicates the picture.
This is why retatrutide 2026 trial data cannot be read as a single number. The molecule interacts differently with each population's underlying physiology.
"The triple-agonist profile means the drug is, in effect, doing different work in different people, and results should always be interpreted through that lens."
Researchers interested in sourcing this compound for further study may explore options such as GLP-3 Reta 10mg or the GLP-3 Reta 20mg GA5 formulation.
Interpreting TRIUMPH-1 and Obesity-Only Population Results

The TRIUMPH-1 trial enrolled adults with obesity who did not have type 2 diabetes. At 80 weeks, participants on the highest retatrutide dose achieved weight reductions described by investigators as "unprecedented", well above the 20% threshold that had long been considered aspirational for pharmacotherapy.
Several variables explain why this population produced the most striking numbers:
- Higher baseline BMI means more absolute weight available to lose, inflating percentage figures in some analyses.
- Intact incretin sensitivity allows both GLP-1 and GIP pathways to function at full efficiency.
- Longer follow-up (80 weeks) captures the full arc of weight loss, which continues past the plateaus typically seen at 24-36 weeks in shorter trials.
- Aggressive dose escalation was feasible in this group due to lower baseline gastrointestinal comorbidity burden.
Readers comparing these results to earlier 24-week or 36-week trials, even within the same program, should expect significantly lower percentage weight loss in shorter studies simply due to follow-up duration. This is not a drug failure; it is a timeline artifact.
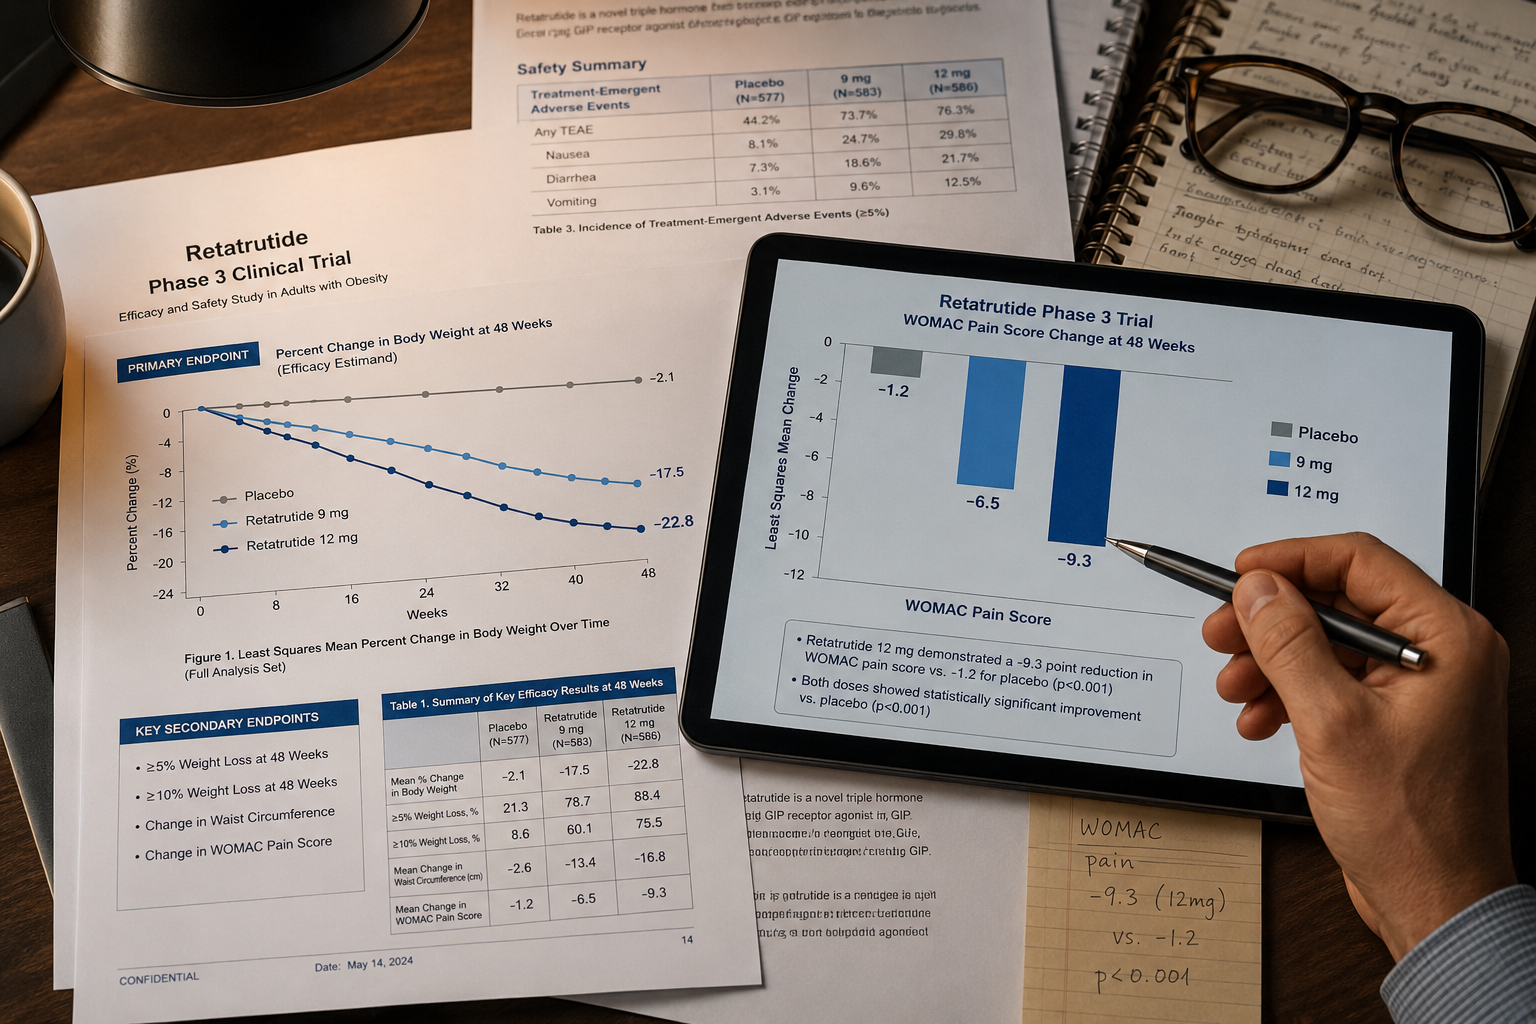
The obesity plus knee osteoarthritis sub-study added another dimension: participants showed clinically meaningful improvements in pain scores and physical function alongside weight loss. This suggests the cardiometabolic and mechanical burden of obesity is addressable simultaneously, though attributing functional improvements purely to weight loss versus direct anti-inflammatory effects remains an open research question.
Reading Results in Type 2 Diabetes and Cardiovascular-Risk Populations
When retatrutide was studied in people with obesity or overweight and concurrent type 2 diabetes, the weight loss remained robust, meaningfully exceeding outcomes from approved GLP-1 agents, while A1C reductions were substantial. However, absolute weight loss was modestly lower than in the non-diabetic obesity cohort.
Three reasons explain this gap:
- Blunted GIP response is common in long-standing type 2 diabetes, reducing one of the three receptor contributions.
- Baseline medications, including insulin and sulfonylureas, may independently promote weight retention.
- Conservative dose escalation is often applied in diabetic populations to manage hypoglycemia risk, limiting peak exposure.
For cardiovascular-risk populations, the picture in 2026 remains partially incomplete. Cardiometabolic risk markers, including LDL cholesterol, triglycerides, blood pressure, waist circumference, and high-sensitivity CRP, all moved in favorable directions across trials. These are meaningful intermediate endpoints, but a dedicated cardiovascular outcomes trial (CVOT) reporting hard events such as MACE has not yet produced final data as of late 2026.
This is the single most important caveat for high-risk populations: improved risk factors do not automatically equal reduced events. Readers and clinicians should treat cardiovascular intermediate data as hypothesis-generating, not confirmatory.
Comparing Retatrutide to Existing GLP-1 and Dual-Agonist Drugs
| Factor | GLP-1 Mono-agonist | Dual GLP-1/GIP | Retatrutide (Triple) |
|---|---|---|---|
| Receptor targets | 1 | 2 | 3 |
| Peak weight loss (approx.) | 12-15% | 18-22% | 24%+ (non-diabetic, 80wk) |
| A1C reduction | Strong | Strong | Strong |
| CVOT data available | Yes (select agents) | Partial | Pending |
| Energy expenditure effect | Modest | Moderate | Elevated (glucagon) |
Industry analysts broadly expect regulatory submissions to follow completion of the TRIUMPH program, though timelines remain subject to trial completion and regulatory review.
Those researching retatrutide for scientific purposes can find formulation options including GLP-3 Reta CAG 10mg GA5 and may also want to review peptide supplier comparisons when evaluating sourcing quality. Additional product options are listed under Reta peptide for sale and buy Reta online.
Safety Profile Across Populations
The tolerability profile across retatrutide trials is broadly consistent with the GLP-1 drug class: nausea, vomiting, and diarrhea are the most common adverse events, are dose-dependent, and largely resolve after the titration phase. No unexpected safety signals have emerged across the populations studied. The glucagon component raised theoretical concerns about hepatic glucose output and lean mass loss; neither has materialized as a clinically significant issue in trial data to date.
Conclusion
Retatrutide 2026 trial data represents a genuine advance in obesity and metabolic pharmacotherapy. The triple-agonist mechanism produces weight loss and cardiometabolic improvements that exceed any approved agent, but those results are inseparable from the populations that generated them.
Actionable steps for readers and clinicians:
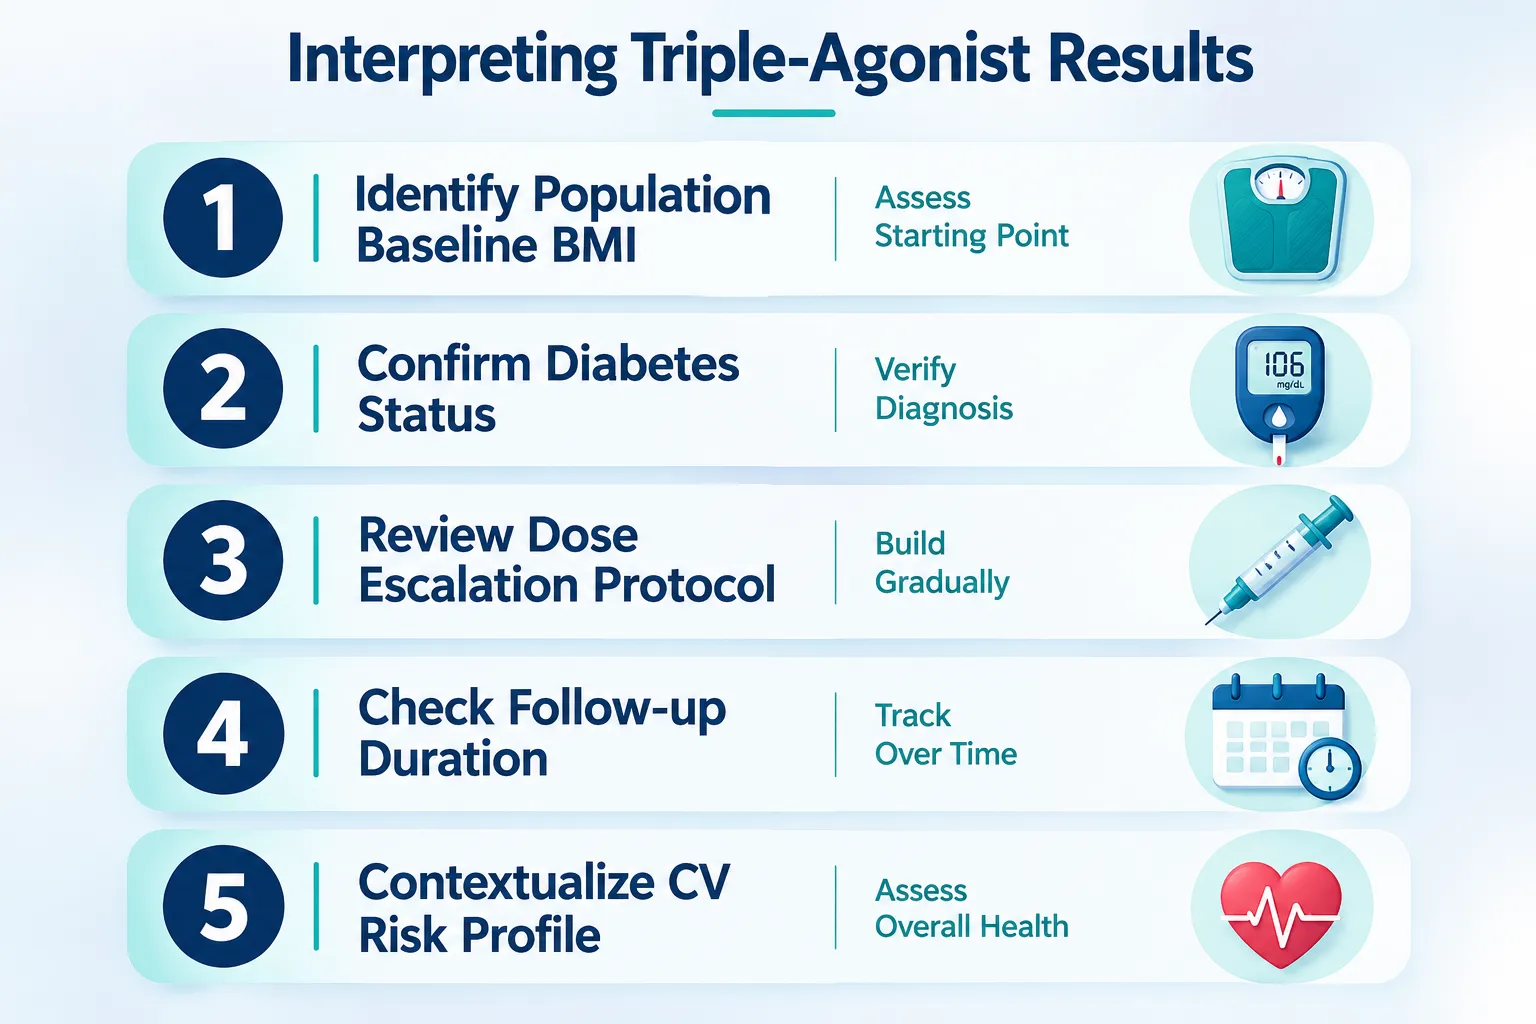
- Always note whether results come from a diabetic or non-diabetic cohort before comparing percentages across trials.
- Confirm the follow-up duration, 80-week data is not comparable to 24-week data even from the same drug.
- Treat cardiovascular risk factor improvements as promising signals, not confirmed outcomes, until CVOT data is published.
- Apply dose escalation context: aggressive titration in a healthy obesity cohort does not predict the same exposure in a high-risk diabetic patient.
- Monitor the TRIUMPH program for final phase 3 readouts, which will anchor the full regulatory and clinical picture.
The story retatrutide is telling in 2026 is compelling. Reading it accurately requires knowing not just what was measured, but who was measured, for how long, and at what dose.