

Liquid IV and Electrolyte Management in Intensive Peptide Studies: How Osmolality Affects GLP-3, MOTS-c, and Growth Hormone Secretagogue Experiments
Osmolality errors in peptide research do not announce themselves, they quietly distort absorption data, inflate variability, and make promising compounds look weaker than they are. As investigators push deeper into metabolic peptide science in 2026, the intersection of Liquid IV and electrolyte management in intensive peptide studies has become a surprisingly practical concern. Understanding how osmolality shapes the behavior of GLP-3, MOTS-c, and growth hormone secretagogue experiments is no longer a footnote, it is a core protocol decision.
Key Takeaways
- Beverage osmolality directly affects intestinal fluid absorption; hypotonic solutions in the 200-260 mmol/kg range produce the greatest net uptake.
- Liquid IV functions as a lower-electrolyte, ORS-range hypotonic drink (~46 mmol/L sodium) that supports rapid plasma volume restoration without excessive sodium loading.
- For outpatient peptide dosing days, hypotonic ORS-style beverages are preferred; inpatient or invasive procedures call for isotonic IV fluids such as lactated Ringer's (~273 mOsm/L).
- No published data directly link beverage osmolality to GLP-3, MOTS-c, or GH secretagogue pharmacokinetics, current guidance extrapolates from ORS and sports hydration science.
- Standardizing pre-dose hydration volume and osmolality is one of the most cost-effective ways to reduce endpoint variability in intensive metabolic peptide trials.
Why Osmolality Is a First-Order Variable in Peptide Research
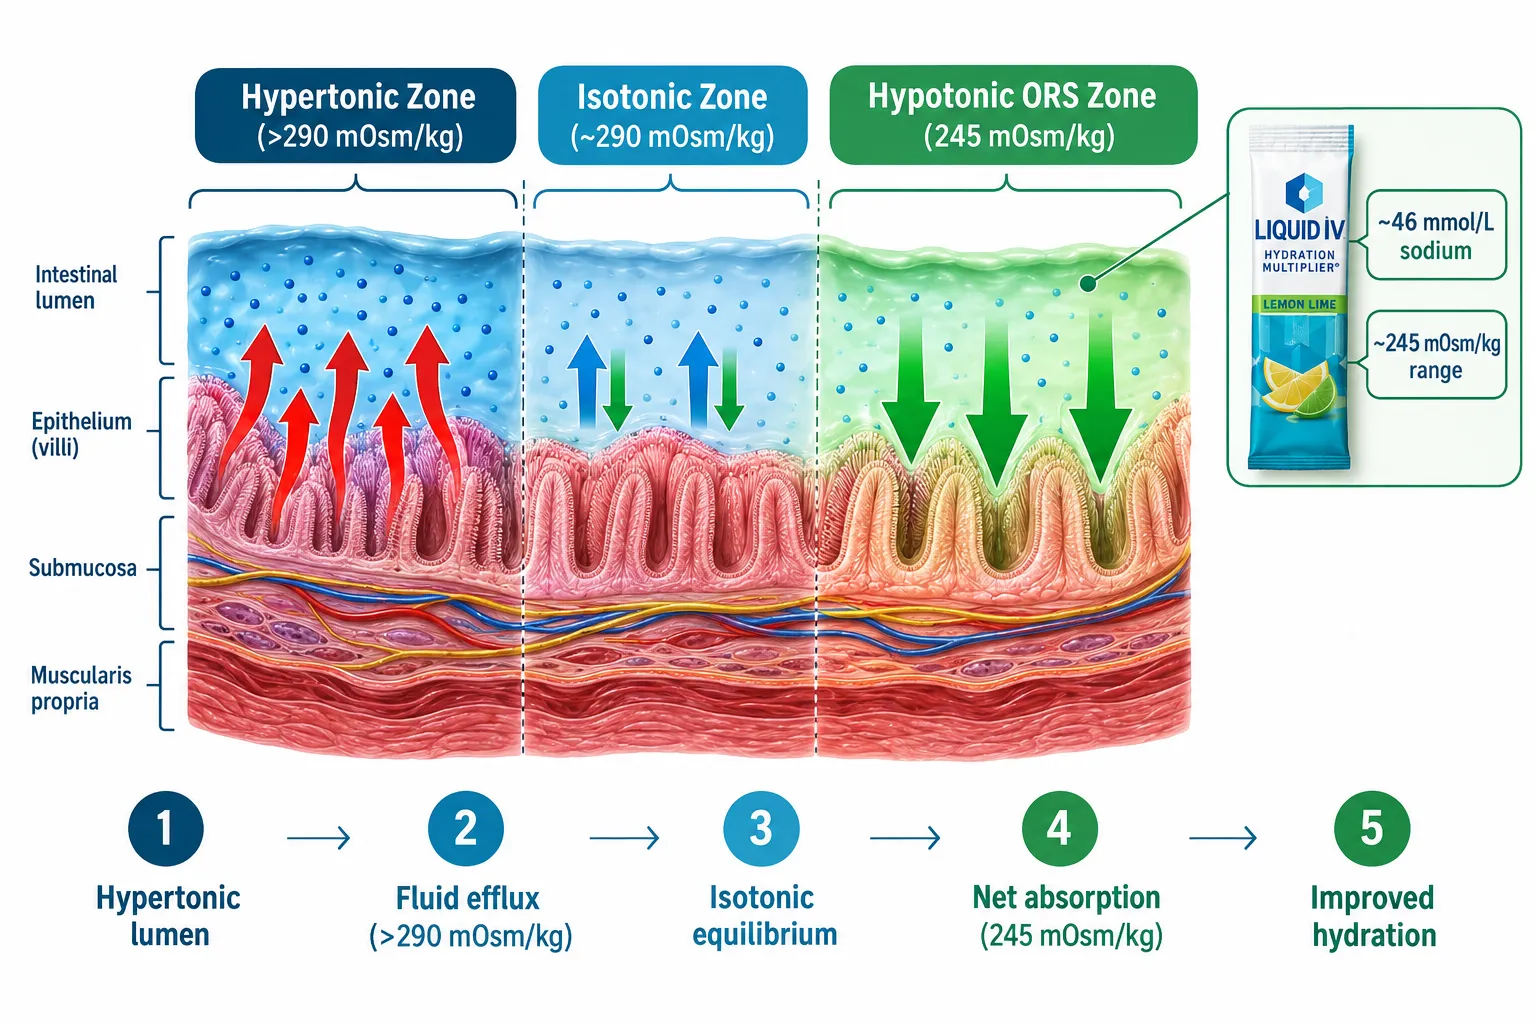
Every solution administered to a research subject, oral or intravenous, carries an osmolality value that the gut and vasculature must reconcile. When that value is mismatched with physiological norms, the consequences ripple through absorption kinetics, intravascular volume, and ultimately the endpoints investigators are trying to measure.
Osmolality vs. tonicity: a critical distinction
These terms are often used interchangeably but are not the same:
| Term | Definition | Practical Example |
|---|---|---|
| Osmolality | Total solute concentration (mmol/kg) | Includes all dissolved particles |
| Tonicity | Effective concentration of non-permeant solutes | Sodium and potassium drive tonicity |
| Osmolarity | Solute concentration per liter (mmol/L) | Used for IV fluid labeling |
Normal saline (0.9% NaCl) carries an osmolarity of approximately 308 mOsm/L, while lactated Ringer's sits near 273 mOsm/L. Pairing peptide infusions with markedly hyperosmolar solutions risks rapid fluid shifts and cellular dehydration, outcomes that confound metabolic endpoints.
The intestinal absorption curve
Research on oral rehydration solutions consistently shows that solutions in the 200-260 mmol/kg range produce the greatest net intestinal fluid absorption. The WHO reduced-osmolarity ORS formulation, 245 mmol/kg total, 75 mmol/L sodium, 75 mmol/L glucose, was specifically redesigned from an earlier 311 mmol/kg formula after perfusion studies demonstrated that the lower osmolality reduced stool output and improved safety. The lesson for peptide researchers: the fluid vehicle matters as much as the peptide itself.
"The fluid vehicle matters as much as the peptide itself, osmolality errors quietly distort absorption data before investigators ever reach their primary endpoint."
Higher carbohydrate concentrations increase beverage osmolality, which in turn slows net intestinal fluid uptake. Gastric emptying can proceed at up to approximately 15-20 mL/min when high gastric volume is maintained with water or dilute carbohydrate solutions, but high-osmolality drinks reduce small-intestinal absorption efficiency rather than dramatically slowing gastric transit. This distinction is important when designing pre-dose hydration windows for oral peptide formulations.
Liquid IV and Electrolyte Management in Intensive Peptide Studies: Profiling the ORS Landscape

Liquid IV Hydration Multiplier is manufacturer-classified as a hypotonic oral rehydration solution, positioned in the ORS range rather than as a conventional sports drink. A standard Lemon Lime stick in 473 mL delivers approximately 500 mg sodium, corresponding to roughly 46 mmol/L, which is about 61% of the WHO reduced-osmolarity ORS sodium level of 75 mmol/L. Its glucose concentration runs approximately 1.7 times the WHO formulation, which nudges osmolality slightly upward compared with minimal-glucose medical ORS, yet the product remains in a hypotonic range overall.
What this profile means for peptide study design:
- Sodium load is modest. At 46 mmol/L, Liquid IV contributes less sodium than standard WHO ORS, making it less likely to perturb plasma sodium in subjects undergoing frequent blood sampling.
- Rapid plasma volume restoration is supported by the hypotonic positioning, which favors net fluid absorption across the gut wall.
- Gastrointestinal distress risk is lower compared with hypertonic sports drinks, which is relevant during caloric restriction protocols common in GLP-3 and growth hormone secretagogue experiments.
For researchers working with GLP-3 peptide compounds or combination formulations such as the GLP3-Reta-CAG 10mg blend, pre-dose hydration standardization using an ORS-range beverage like Liquid IV is a pragmatic approach to reducing absorption variability, even though direct pharmacokinetic data pairing the two remain unpublished as of 2026.
Comparing hydration vehicle options:
| Solution | Approx. Osmolality | Sodium (mmol/L) | Best Use Case |
|---|---|---|---|
| Plain water | ~0 mOsm/kg | 0 | Short, low-intensity sessions |
| Liquid IV (ORS-range) | ~245 mOsm/kg | ~46 | Outpatient dosing days |
| WHO reduced ORS | 245 mmol/kg | 75 | Clinical rehydration |
| Lactated Ringer's (IV) | ~273 mOsm/L | 130 | Inpatient/invasive procedures |
| Normal saline (IV) | ~308 mOsm/L | 154 | Standard IV maintenance |
How Osmolality Affects GLP-3, MOTS-c, and Growth Hormone Secretagogue Experiments
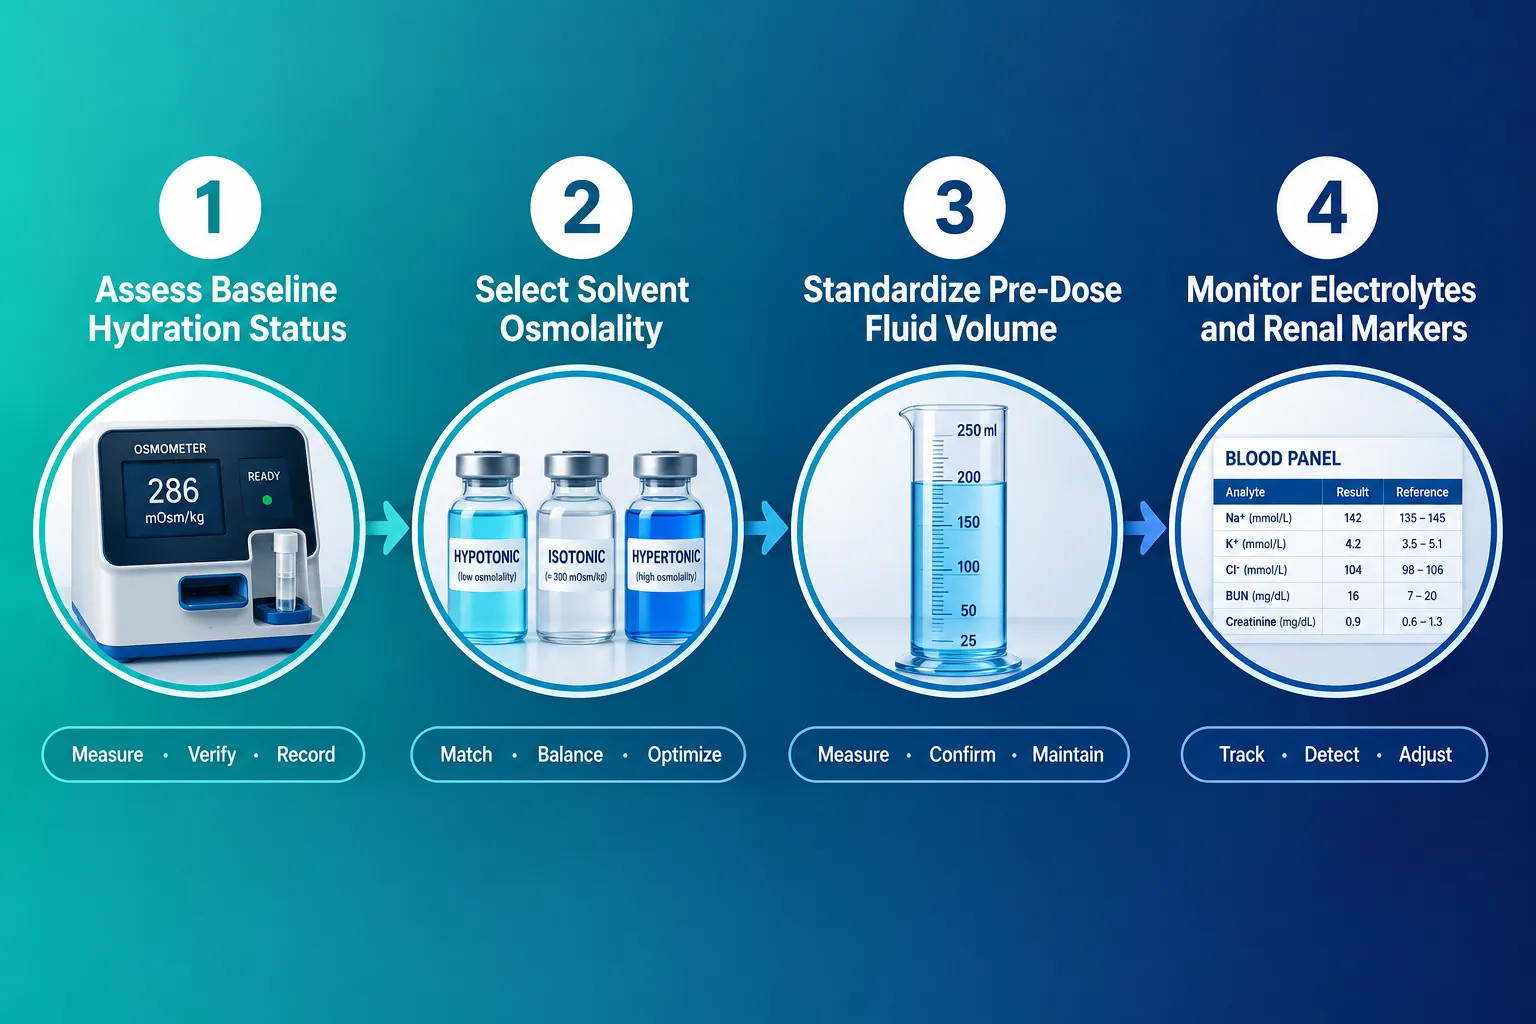
The three peptide classes most actively studied in metabolic research in 2026, GLP-family analogs, mitochondrial-derived MOTS-c, and growth hormone secretagogues, each interact with hydration status through distinct but overlapping mechanisms.
GLP-3 and Gut-Acting Peptide Formulations
GLP-3 receptor agonists act at the intestinal level, making luminal osmotic conditions directly relevant. A hypertonic pre-dose environment can reduce mucosal blood flow and alter enterocyte function, potentially blunting receptor engagement. Investigators sourcing GLP-3R 10mg research peptide or the GLP-3R 30mg format should consider specifying both volume and osmolality of pre-dose fluids in their protocols to limit this confounding variable.
MOTS-c and Mitochondrial Metabolic Endpoints
Native MOTS-c is not FDA-approved, and no large-scale completed human safety trial exists for the native peptide as of mid-2026. CohBar's analog CB4211 completed a phase 1a/1b trial in nonalcoholic fatty liver disease and obesity, showing approximately 21% reduction in ALT and 28% reduction in AST, but hydration protocols in that work followed routine clinical standards rather than purpose-designed ORS regimens.
A new randomized, double-blind, placebo-controlled human trial targeting prediabetes and obesity (often referenced as MOTS-MET) began enrollment in 2026 with 120 planned participants. Its primary endpoints, insulin sensitivity and weight-related measures, are precisely the outcomes most sensitive to hydration-driven volume shifts and electrolyte fluctuations. Researchers exploring MOTS-c and elamipretide relationships should note that fluid and electrolyte monitoring will likely become more tightly controlled as human programs expand.
Growth Hormone Secretagogues and Fluid Dynamics
Growth hormone secretagogue experiments frequently involve overnight fasting, timed blood draws, and caloric restriction, conditions that elevate dehydration risk. Plasma volume contraction can independently elevate GH pulse amplitude, creating a confound if hydration is not standardized. Using a hypotonic ORS-range beverage during outpatient dosing windows, and isotonic IV fluids during inpatient procedures, limits this source of variability. For detailed guidance on peptide dosing considerations, protocol-level decisions about solvent osmolality belong alongside dose and timing parameters.
Key protocol recommendations for 2026 intensive peptide studies:
- Specify pre-dose hydration volume and osmolality in the written protocol, not just "water ad libitum."
- Use hypotonic ORS-range beverages (200-260 mmol/kg) on outpatient dosing days to support absorption and plasma volume.
- Switch to isotonic IV fluids (lactated Ringer's or normal saline) during inpatient or invasive procedures.
- Monitor serum electrolytes and renal markers at baseline and at each major time point.
- Document beverage brand, volume, and timing as a protocol variable, not background noise.
For researchers who want to understand the broader structural context of these peptides before designing hydration protocols, the Peptides 101 for Research-Use Only Buyers resource provides foundational coverage of GLP-3, MOTS-c, and related compounds. Ensuring peptide purity is equally critical, lab tested peptides with verified certificates of analysis reduce the risk of osmolality-independent confounds from impurity loads.
Conclusion
The role of Liquid IV and electrolyte management in intensive peptide studies is not a peripheral concern, it is a protocol-level variable that shapes the reliability of GLP-3, MOTS-c, and growth hormone secretagogue data. Osmolality governs intestinal fluid absorption, intravascular volume, and the stability of metabolic endpoints that these peptides are designed to influence.
Actionable next steps for research teams in 2026:
- Audit existing protocols for any language that leaves pre-dose hydration unspecified.
- Adopt a tiered hydration strategy: hypotonic ORS-range beverages for outpatient days, isotonic IV fluids for inpatient or invasive sessions.
- Treat beverage osmolality as a documented protocol variable alongside dose, route, and timing.
- Monitor serum sodium, potassium, and creatinine at each major sampling point to detect hydration-driven confounds early.
- As human MOTS-c and GLP-family trials scale beyond phase 1, advocate for standardized hydration annexes in published protocols to enable cross-study comparisons.
The data directly linking Liquid IV's osmolality profile to peptide pharmacokinetics do not yet exist, but the physiological logic is sound, the ORS science is robust, and the cost of standardizing hydration is far lower than the cost of unexplained endpoint variability.