Meloxicam and Tissue-Repair Peptides: Comparing Nonsteroidal Anti-Inflammatory Drugs with BPC-157 in In Vitro Models
COX-2 inhibition and growth factor upregulation are not two sides of the same coin, they are mechanistically opposite strategies for managing tissue injury. This fundamental difference sits at the center of any rigorous comparison of meloxicam and tissue-repair peptides: comparing nonsteroidal anti-inflammatory drugs with BPC-157 in in vitro models. As cell culture research grows more sophisticated in 2026, the contrast between these two approaches has become sharper, more clinically relevant, and more debated.
Key Takeaways
- Meloxicam reduces inflammation primarily by blocking COX-2 enzymes and suppressing prostaglandin synthesis, which may also dampen early repair signaling.
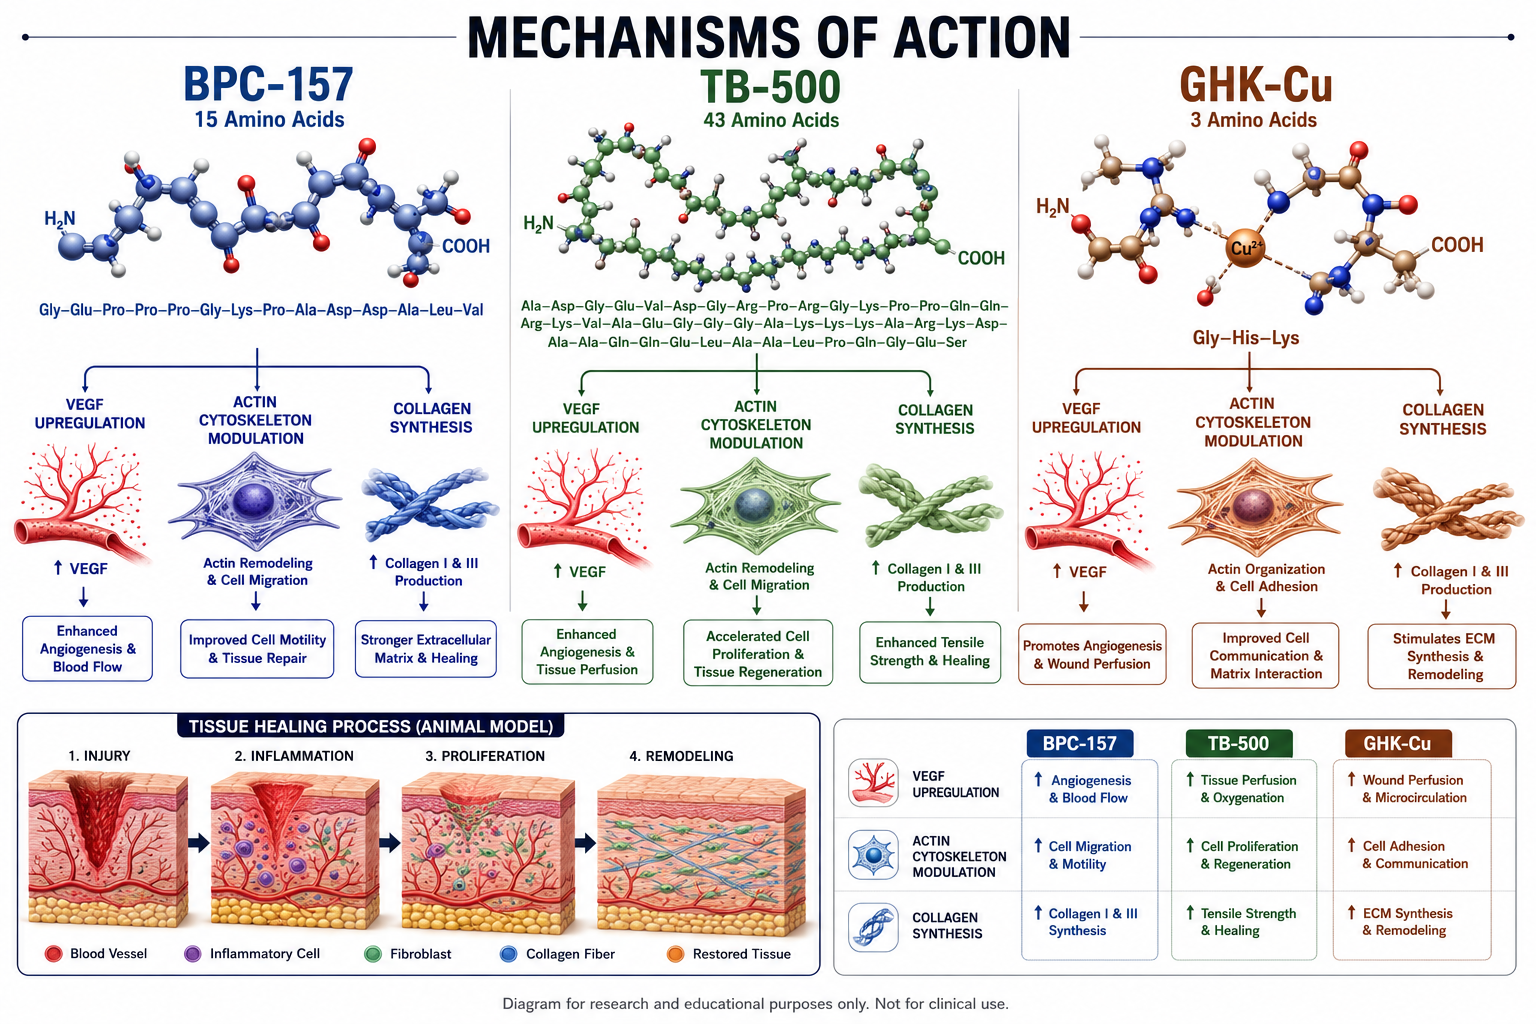
- BPC-157 is a pleiotropic tissue-repair peptide that activates VEGFR2, the Akt-eNOS nitric oxide axis, and promotes fibroblast activity, collagen deposition, and angiogenesis.
- In vitro musculoskeletal models consistently show BPC-157 enhancing tenocyte survival, fibroblast migration, and growth hormone receptor expression.
- NSAIDs such as meloxicam have been repeatedly associated with reduced collagen synthesis in preclinical models, contrasting with BPC-157's repair-promoting profile.
- BPC-157 remains a research-only compound without major regulatory approval; meloxicam is a fully approved NSAID with no clinical indication for tissue regeneration.
How COX-2 Inhibition and Peptide Signaling Differ at the Cellular Level
Understanding the mechanistic gap between meloxicam and BPC-157 starts at the receptor level.
Meloxicam is a COX-2-preferential NSAID. It works by blocking cyclooxygenase-2 enzymes, which halts the conversion of arachidonic acid into prostaglandins. This reduces pain and swelling efficiently. However, prostaglandins also serve as early-phase messengers that recruit repair cells to damaged tissue. When that signal is suppressed, the downstream cascade of fibroblast recruitment, collagen synthesis, and angiogenesis can be partially blunted.
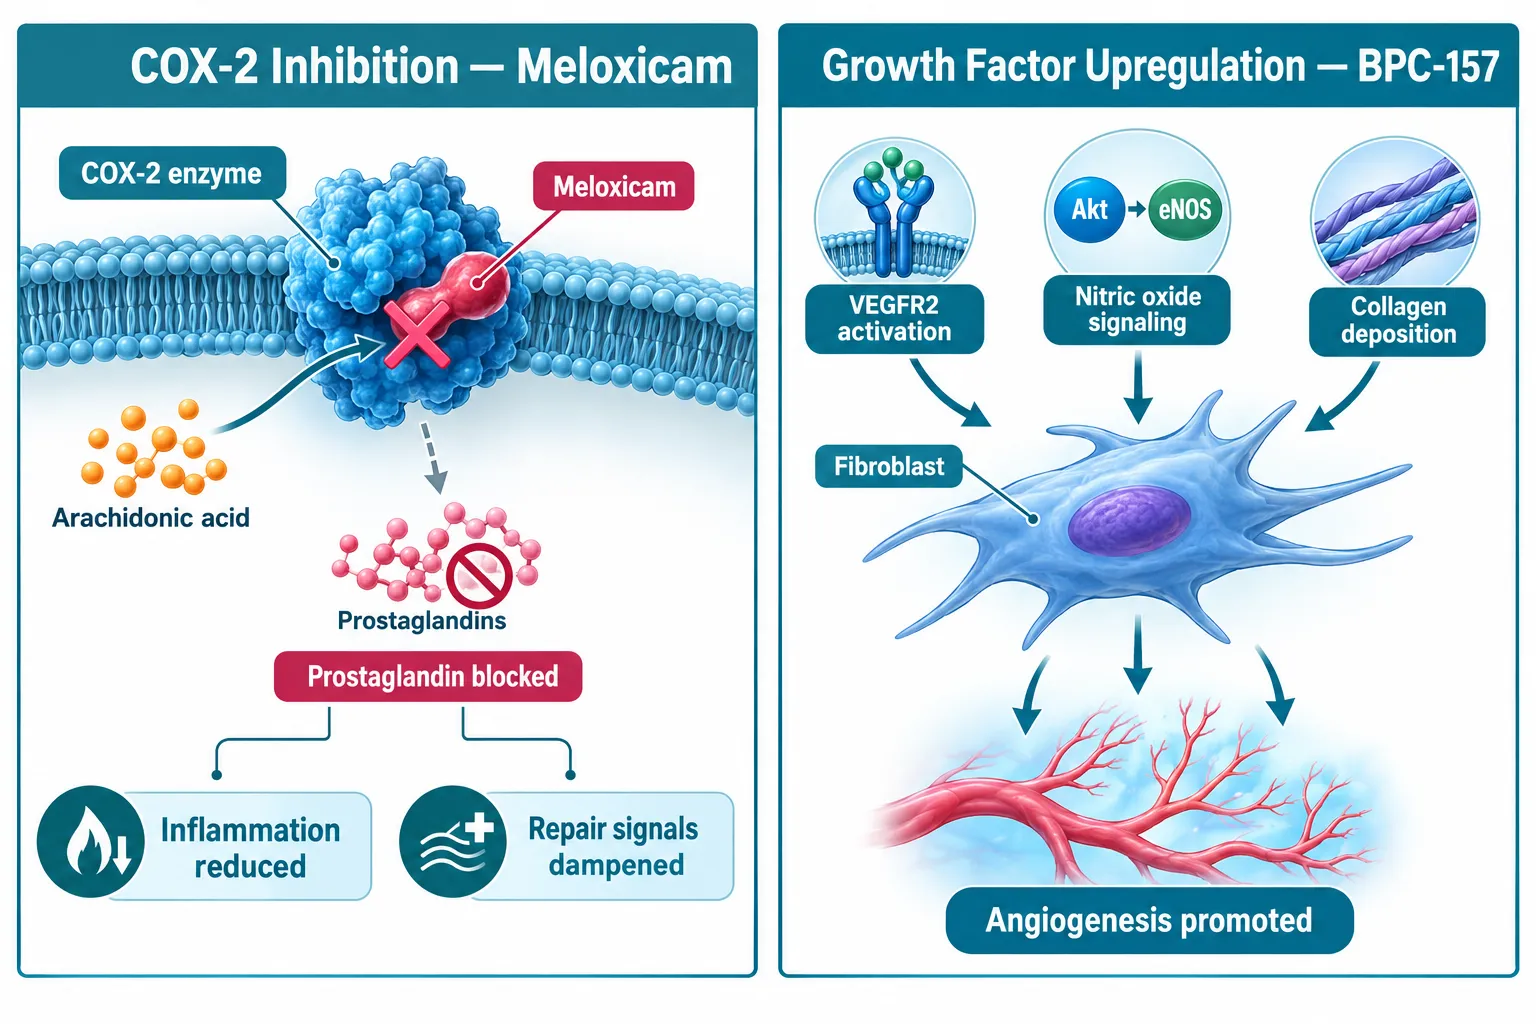
BPC-157, by contrast, operates through an entirely different set of molecular targets. It activates VEGFR2 (vascular endothelial growth factor receptor 2) and the Akt-eNOS nitric oxide pathway, which directly promotes new blood vessel formation and cell survival. It also upregulates growth hormone receptors on fibroblasts and tenocytes, enhancing their proliferative and migratory capacity. Rather than silencing an inflammatory cascade, BPC-157 accelerates the transition from injury to active repair.
Key distinction: Meloxicam turns down the inflammatory signal. BPC-157 turns up the repair signal. These are not equivalent actions.
This mechanistic separation is why researchers studying meloxicam and tissue-repair peptides in cell culture systems often find these two compounds occupying non-overlapping functional roles rather than competing for the same outcome.
What In Vitro Models Reveal About BPC-157 and NSAID Effects on Tissue Repair
Cell culture studies have produced some of the clearest evidence for BPC-157's repair-promoting properties.
In rat Achilles tenocyte cultures, BPC-157 exposure consistently produces enhanced cell survival and proliferation. Fibroblast cultures treated with BPC-157 show increased growth hormone receptor expression, which correlates with improved collagen fiber organization. Wound-healing scratch assays demonstrate accelerated cell migration into the injury zone, and angiogenesis assays confirm increased tubule formation in endothelial cell models.
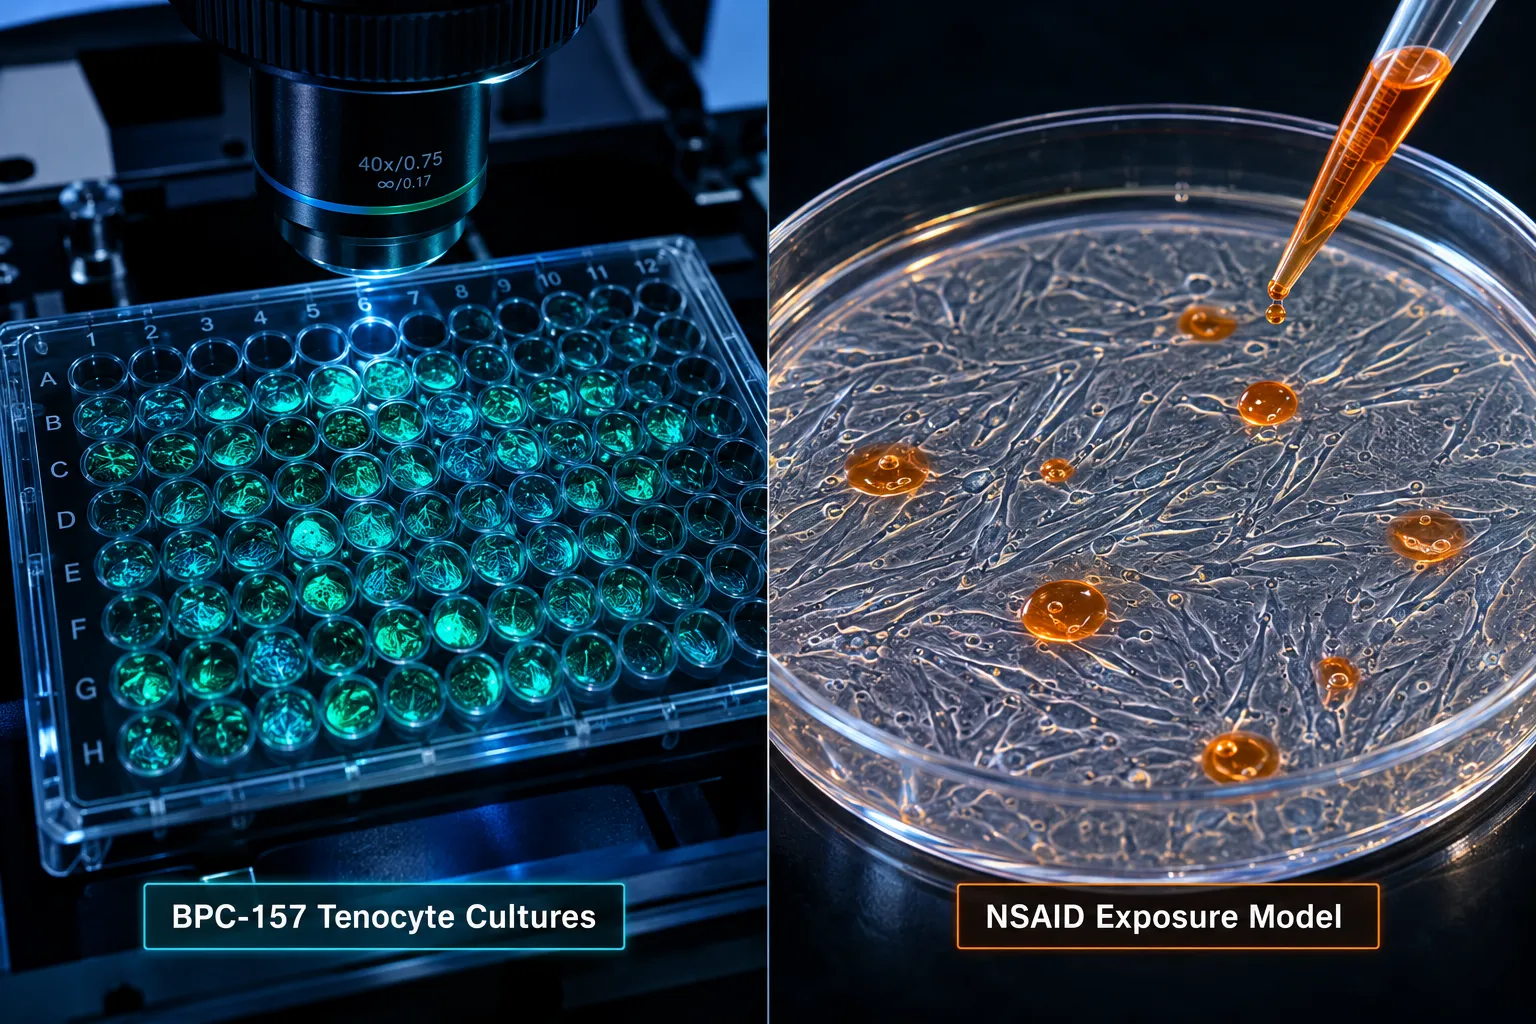
NSAIDs tell a different story in the same types of models. Multiple preclinical musculoskeletal studies, including a 2026 systematic overview of 36 studies, have linked conventional NSAID use to reduced collagen synthesis and slower long-term structural healing. Ibuprofen and naproxen are the most cited examples, but the COX-2 inhibition mechanism shared with meloxicam raises similar theoretical concerns for repair-focused endpoints.
Summary of in vitro findings:
| Compound | Primary Mechanism | Effect on Collagen | Effect on Angiogenesis | Effect on Fibroblast Activity |
|---|---|---|---|---|
| Meloxicam | COX-2 inhibition | Potentially reduced | Neutral to negative | Minimal direct effect |
| BPC-157 | VEGFR2 / Akt-eNOS activation | Enhanced | Strongly promoted | Significantly increased |
A particularly compelling area of in vitro research involves gastrointestinal cell models. BPC-157 has repeatedly protected gastric and intestinal mucosal cells from NSAID-induced damage in rat studies, positioning it as a cytoprotective reference compound rather than an NSAID substitute. For researchers exploring SS-31 peptides for sale or other mitochondria-targeted compounds, this cytoprotective angle offers a useful parallel framework.
Practical Research Considerations When Comparing NSAIDs with BPC-157 in Cell Culture Systems
Designing in vitro experiments that meaningfully compare meloxicam and tissue-repair peptides: comparing nonsteroidal anti-inflammatory drugs with BPC-157 in in vitro models requires careful attention to endpoint selection, dosing protocols, and timing.
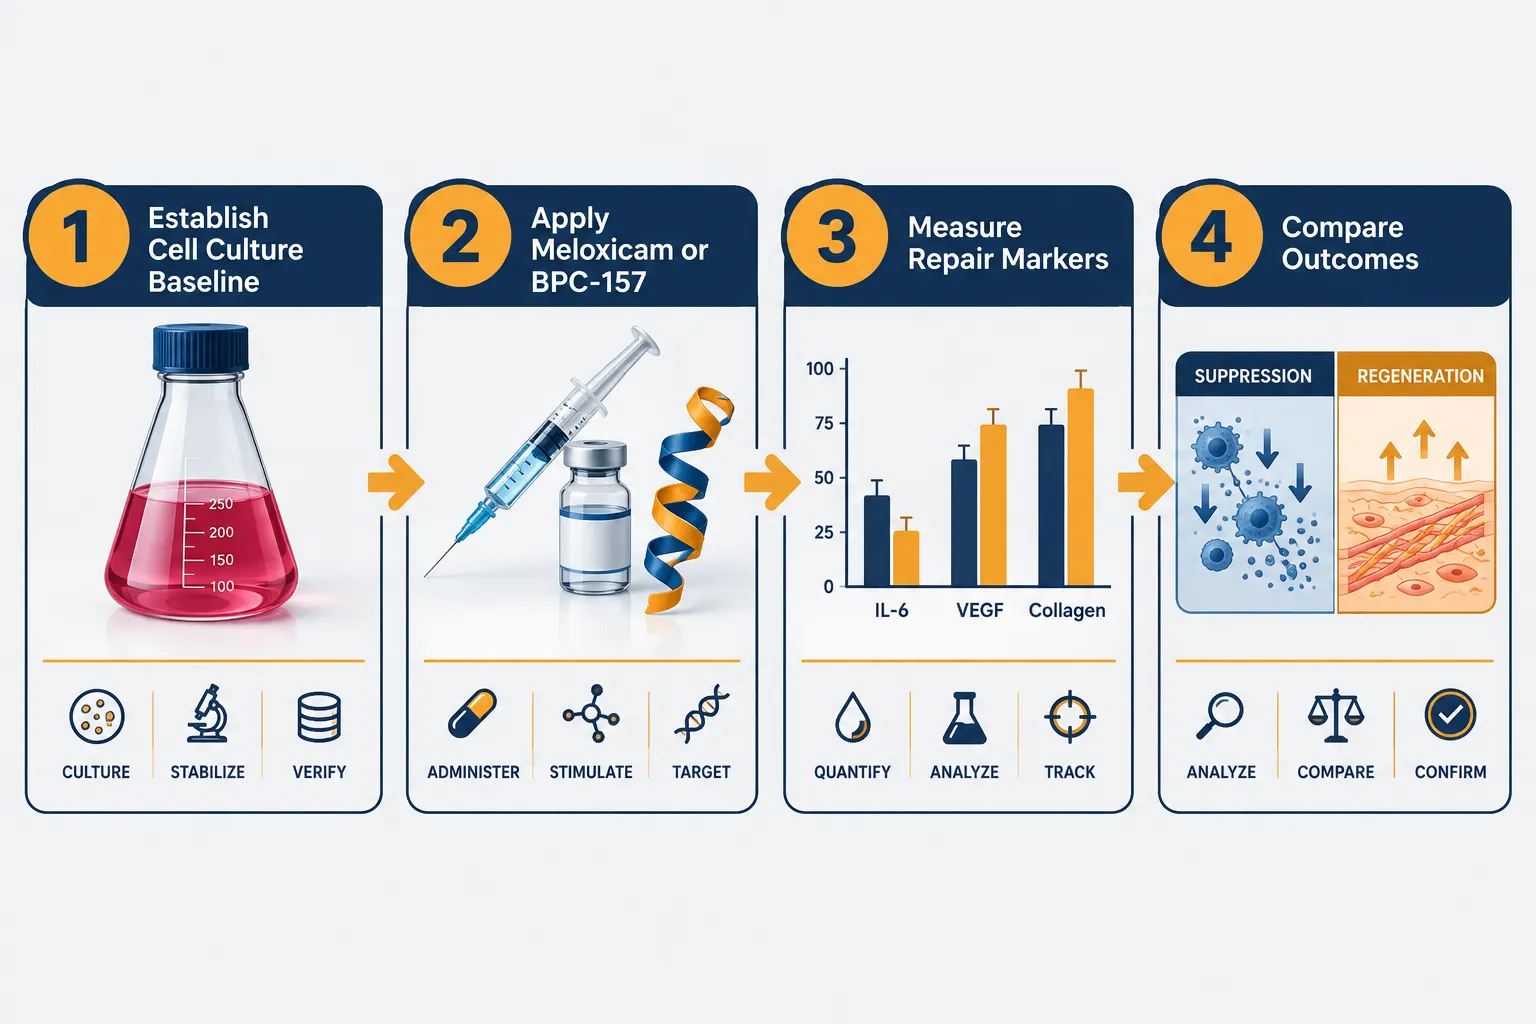
Key design considerations include:
- Endpoint selection: If the primary endpoint is inflammation suppression (IL-6, TNF-alpha, PGE2), meloxicam performs reliably. If the endpoint is structural repair (collagen density, cell migration rate, VEGF expression), BPC-157 is the mechanistically appropriate comparator.
- Timing of compound exposure: COX-2 inhibition is most relevant in the early inflammatory phase. BPC-157's growth-factor-driven effects are most active during the proliferative and remodeling phases. Applying both simultaneously may produce conflicting signals.
- Concentration calibration: BPC-157 research protocols for gut and NSAID-induced damage models typically span 4-6 weeks in animal studies; in vitro timelines should account for the compound's mechanism of action rather than simply mirroring NSAID dosing schedules.
Researchers working with multiple peptide classes, such as those exploring GHK-Cu peptide for skin and connective tissue models, or reviewing CJC-1295 pharmacokinetic comparisons for growth hormone axis research, will recognize that peptide-driven repair signaling requires different experimental frameworks than small-molecule anti-inflammatory drugs.
One 2026 molecular docking study identified FER, TUBA1B, and MICAL2 as proteins where meloxicam shows strong in silico binding affinity, suggesting possible cytoskeletal and signaling roles beyond prostaglandin suppression. However, these findings remain computational and have not yet been validated in dedicated cell culture assays.
Regulatory context matters: BPC-157 is currently a research-only compound under ongoing regulatory review, while meloxicam is a fully approved NSAID. Researchers combining them in experimental settings should note that continuous COX-2 inhibition may theoretically blunt BPC-157's growth-factor-driven repair signaling. Using the lowest effective NSAID dose and avoiding around-the-clock administration during BPC-157 protocols is a commonly recommended precaution when structural repair is the primary endpoint.
Those exploring complementary peptide combinations may also find value in reviewing the synergy of LL-37 and SS-31 for additional context on how peptide combinations interact in repair-focused models. Similarly, researchers studying metabolic and hormonal contexts alongside tissue repair may reference Tesamorelin and Ipamorelin combination safety considerations as a model for responsible multi-compound research design.
For those sourcing research-grade compounds, wholesale peptides with verified purity documentation are essential for reproducible in vitro results.
Conclusion
The comparison of meloxicam and tissue-repair peptides: comparing nonsteroidal anti-inflammatory drugs with BPC-157 in in vitro models ultimately reveals two compounds with fundamentally different roles in tissue biology. Meloxicam is a well-characterized, clinically approved tool for reducing prostaglandin-mediated inflammation, effective, predictable, but limited in its capacity to actively drive structural repair. BPC-157 is a pleiotropic research peptide that promotes angiogenesis, collagen deposition, and fibroblast activity through growth factor pathways, offering a mechanistically distinct and potentially complementary profile.
Actionable next steps for researchers:
- Define repair-specific endpoints (VEGF, collagen, cell migration) separately from inflammation endpoints (IL-6, COX-2, PGE2) in study design.
- Avoid applying NSAID dosing logic to BPC-157 protocols; align exposure timing with the compound's mechanism of action.
- Treat computational findings (such as meloxicam's docking affinity to cytoskeletal proteins) as hypothesis-generating, not conclusive.
- Source third-party tested, purity-verified peptides to ensure experimental reproducibility.
- Monitor the regulatory landscape for BPC-157, as its status continues to evolve in 2026.
The field is moving toward a clearer understanding that analgesia with suppression and analgesia with repair are not interchangeable goals, and that in vitro models are the most precise tool available for distinguishing between them.