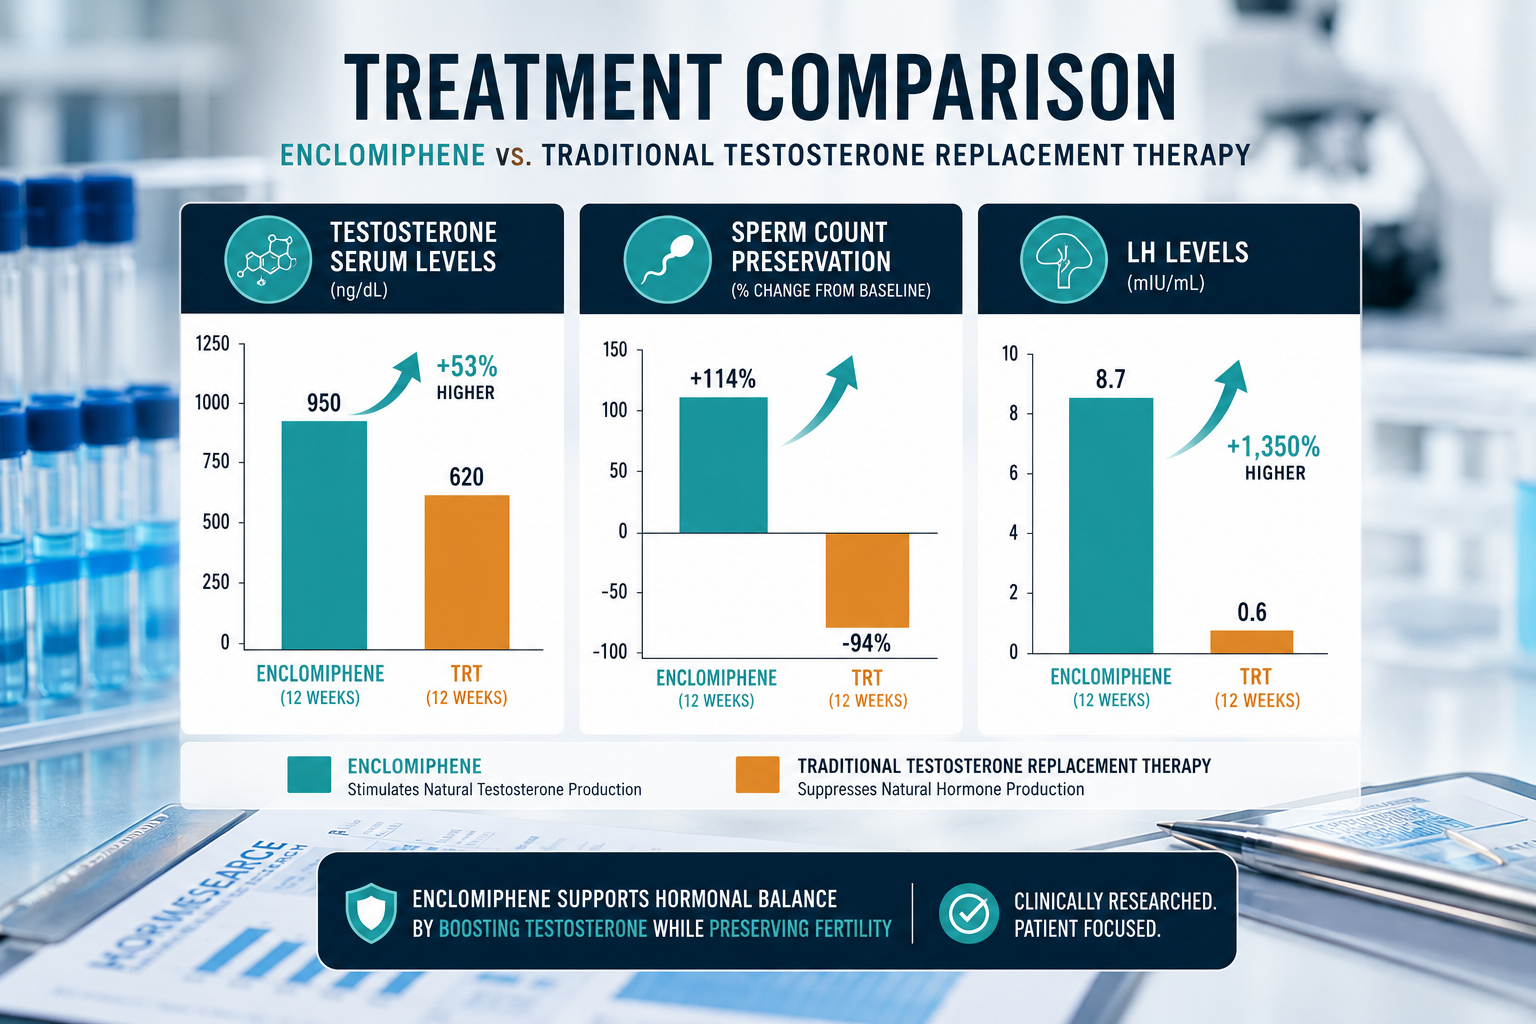
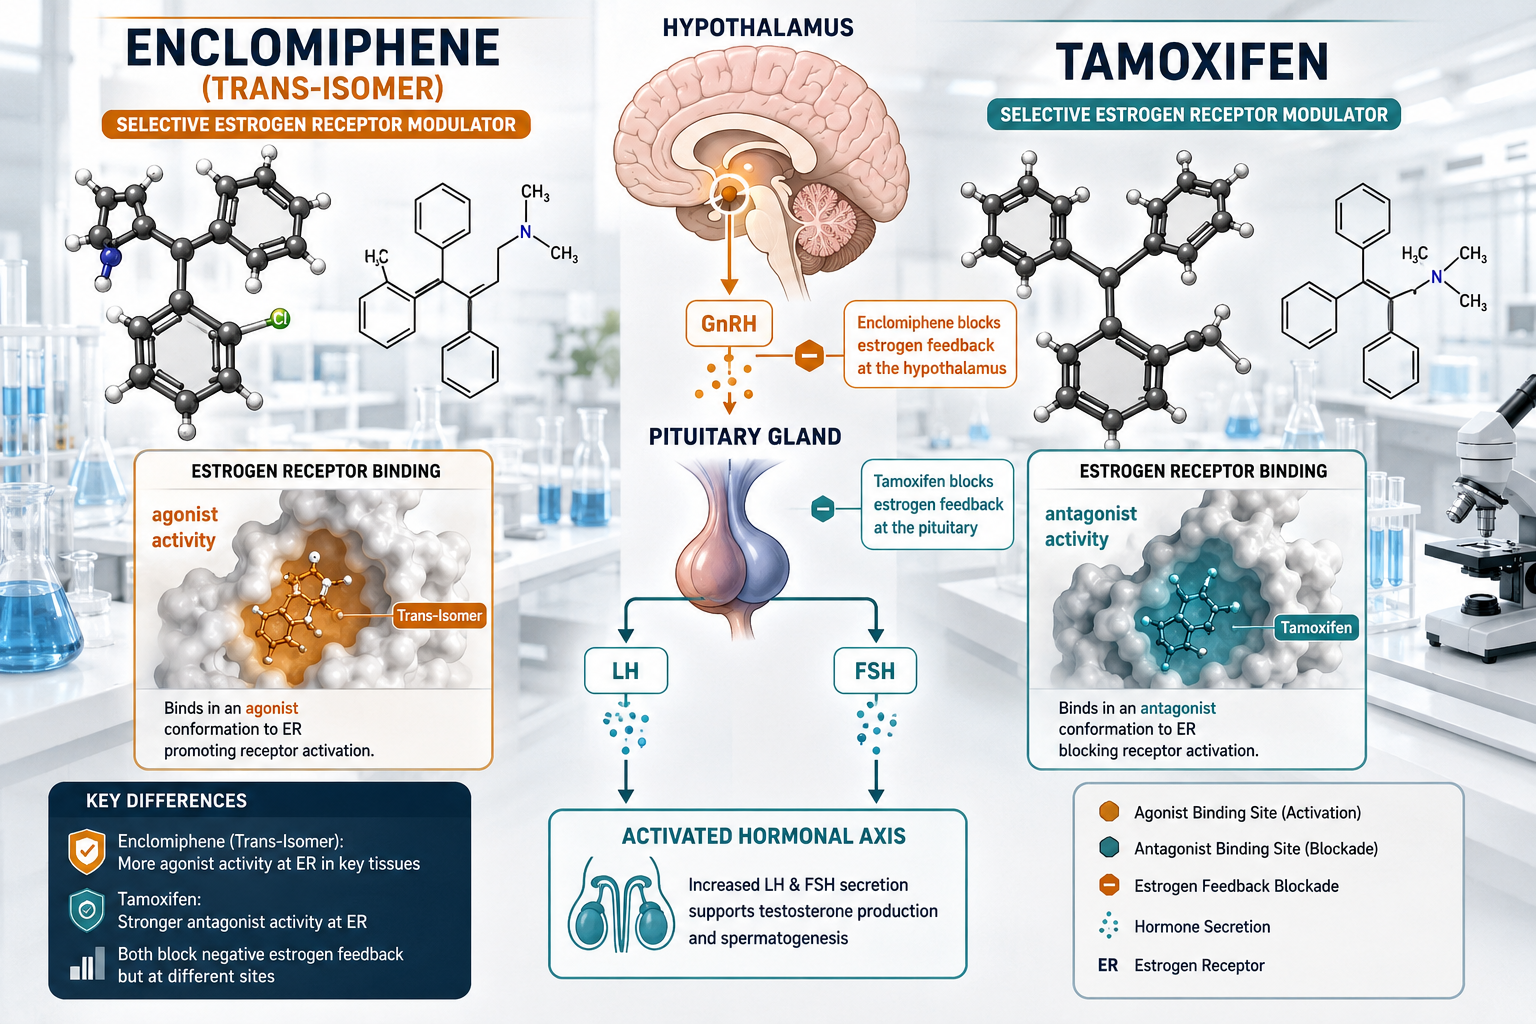
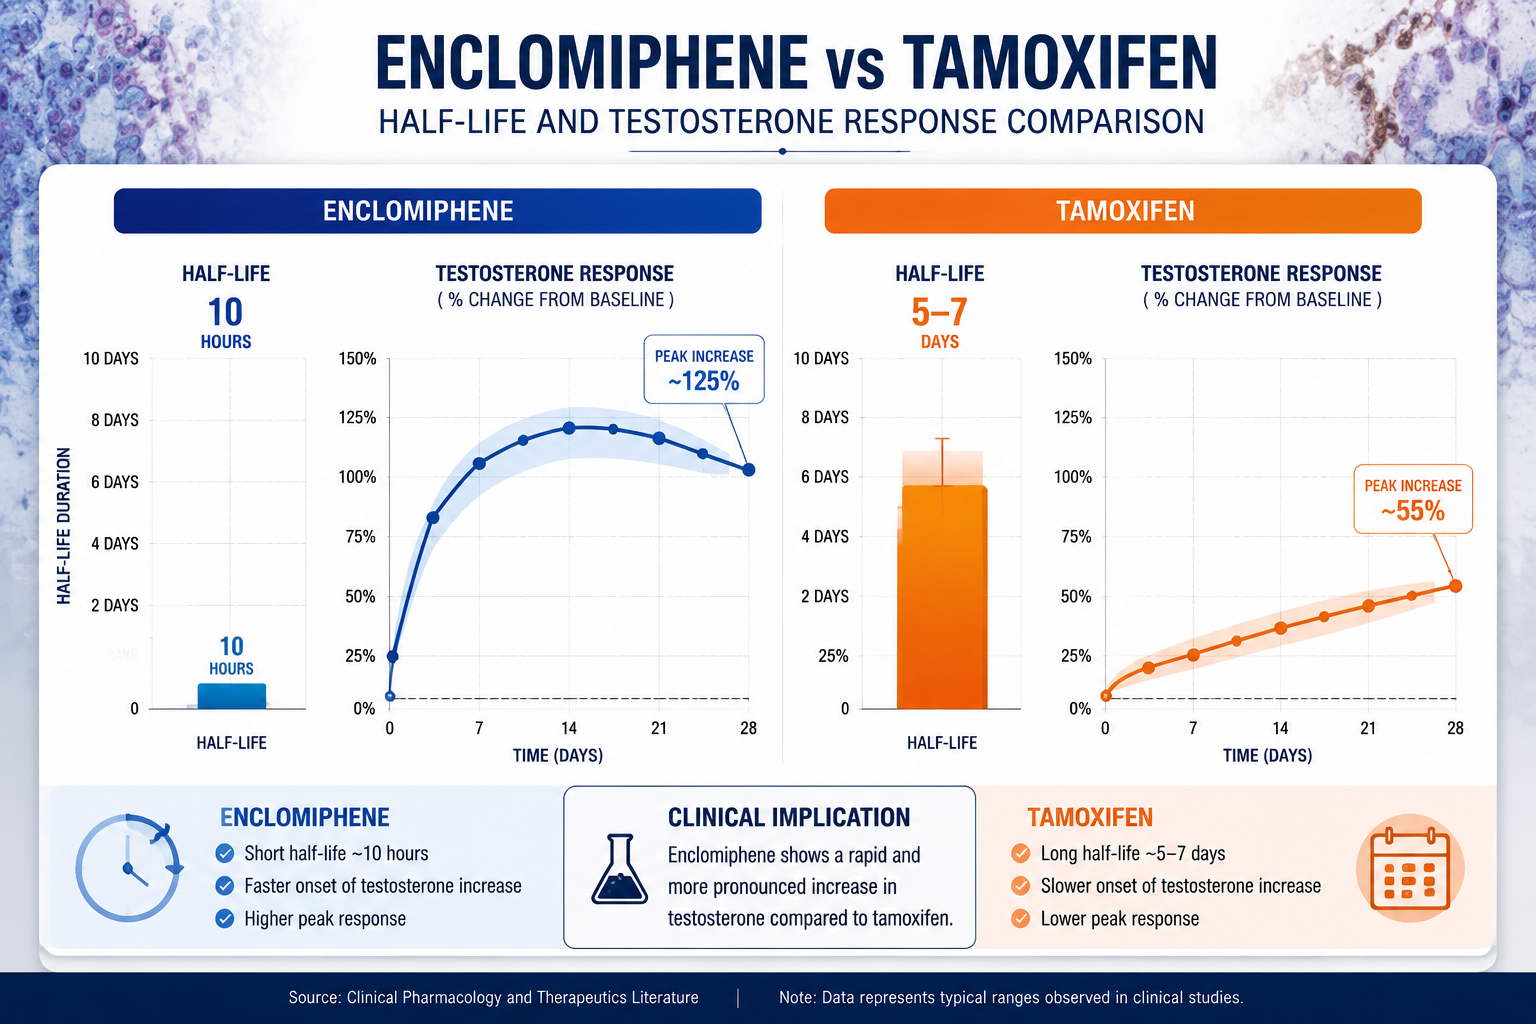
Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: male fertility research

Finasteride and Enclomiphene Co-Administration: Evaluating DHT, LH Pulsatility, and Spermatogenesis in Rodent Models

Finasteride and Enclomiphene Co-Administration: Evaluating DHT, LH Pulsatility, and Spermatogenesis in Rodent Models

October 27, 2026/0 Comments/in Uncategorized/by

Blocking 5-alpha reductase while simultaneously stimulating gonadotropin release creates a biochemical tension that preclinical researchers have not yet formally mapped. As of 2026, no published rodent study has directly examined finasteride and enclomiphene co-administration with concurrent measurement of DHT, LH pulsatility, and spermatogenesis, yet the mechanistic logic for doing so is compelling. Understanding how 5-alpha reductase inhibitors modify endocrine feedback loops when evaluating enclomiphene citrate gonadal restoration protocols is the central challenge this research gap presents.

Key Takeaways

  • No published rodent model to date has simultaneously tested finasteride and enclomiphene co-administration while tracking DHT, LH pulse dynamics, and spermatogenesis.
  • Finasteride suppresses conversion of testosterone to DHT, which preclinical data links to impaired spermatogenic recovery even when serum testosterone is preserved or elevated.
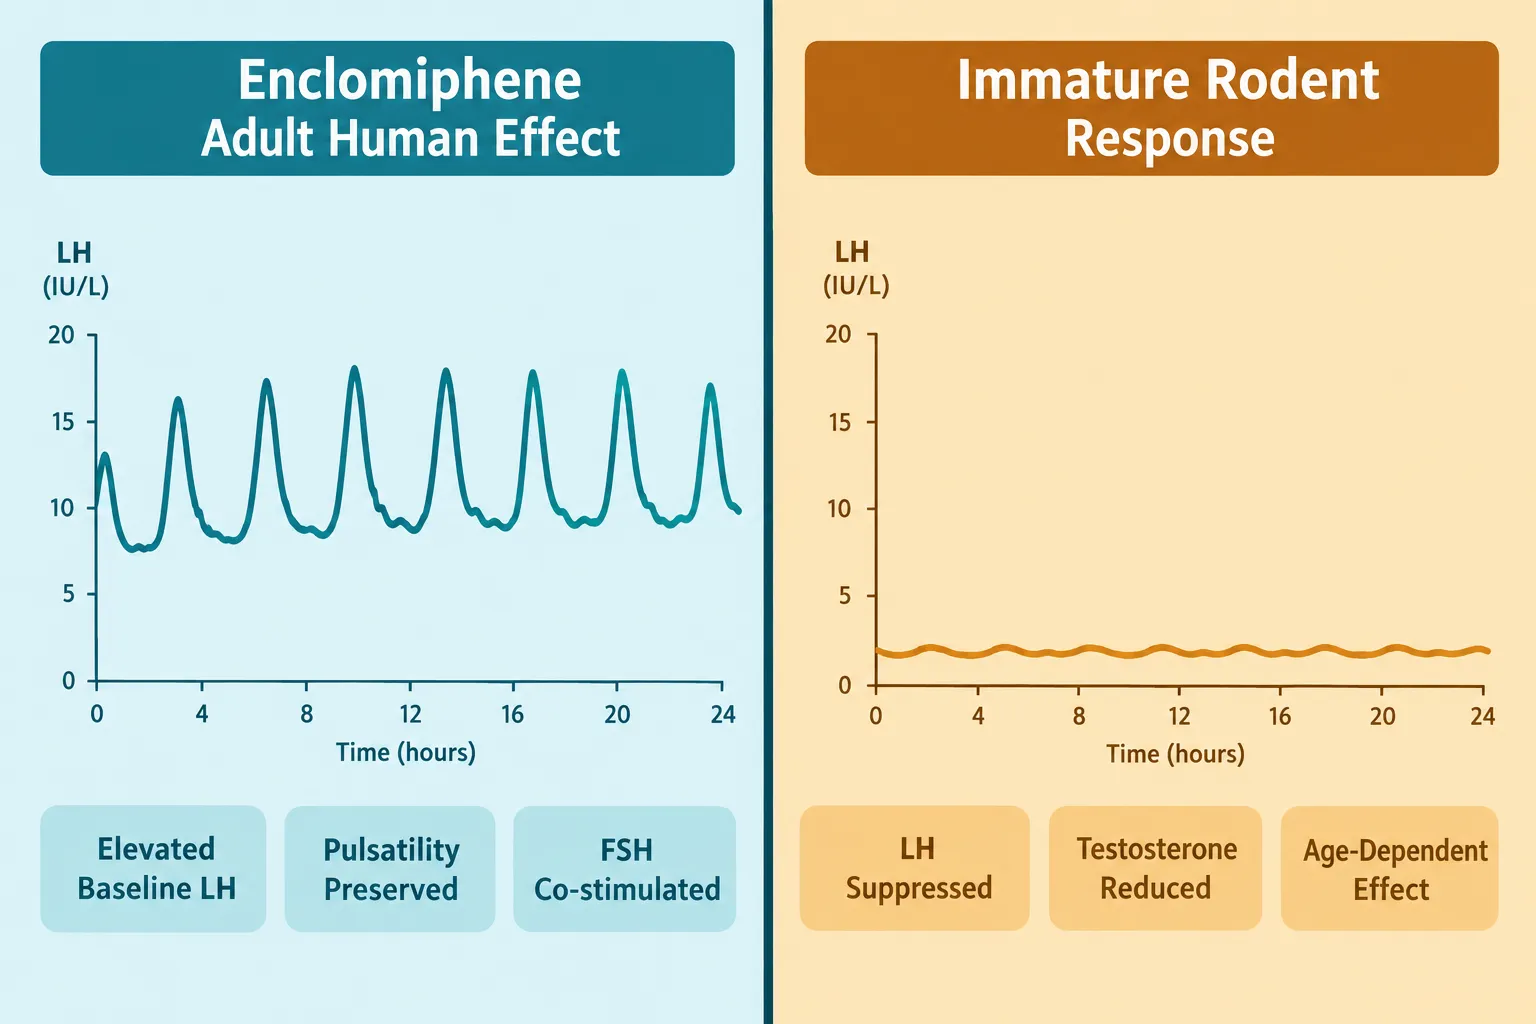
  • Enclomiphene's effect on LH is age- and species-dependent: it elevates LH in adult humans but suppresses it in immature rodents at certain doses.
  • Co-administration could produce elevated systemic testosterone alongside reduced intratesticular DHT, a combination with unpredictable net effects on sperm production.
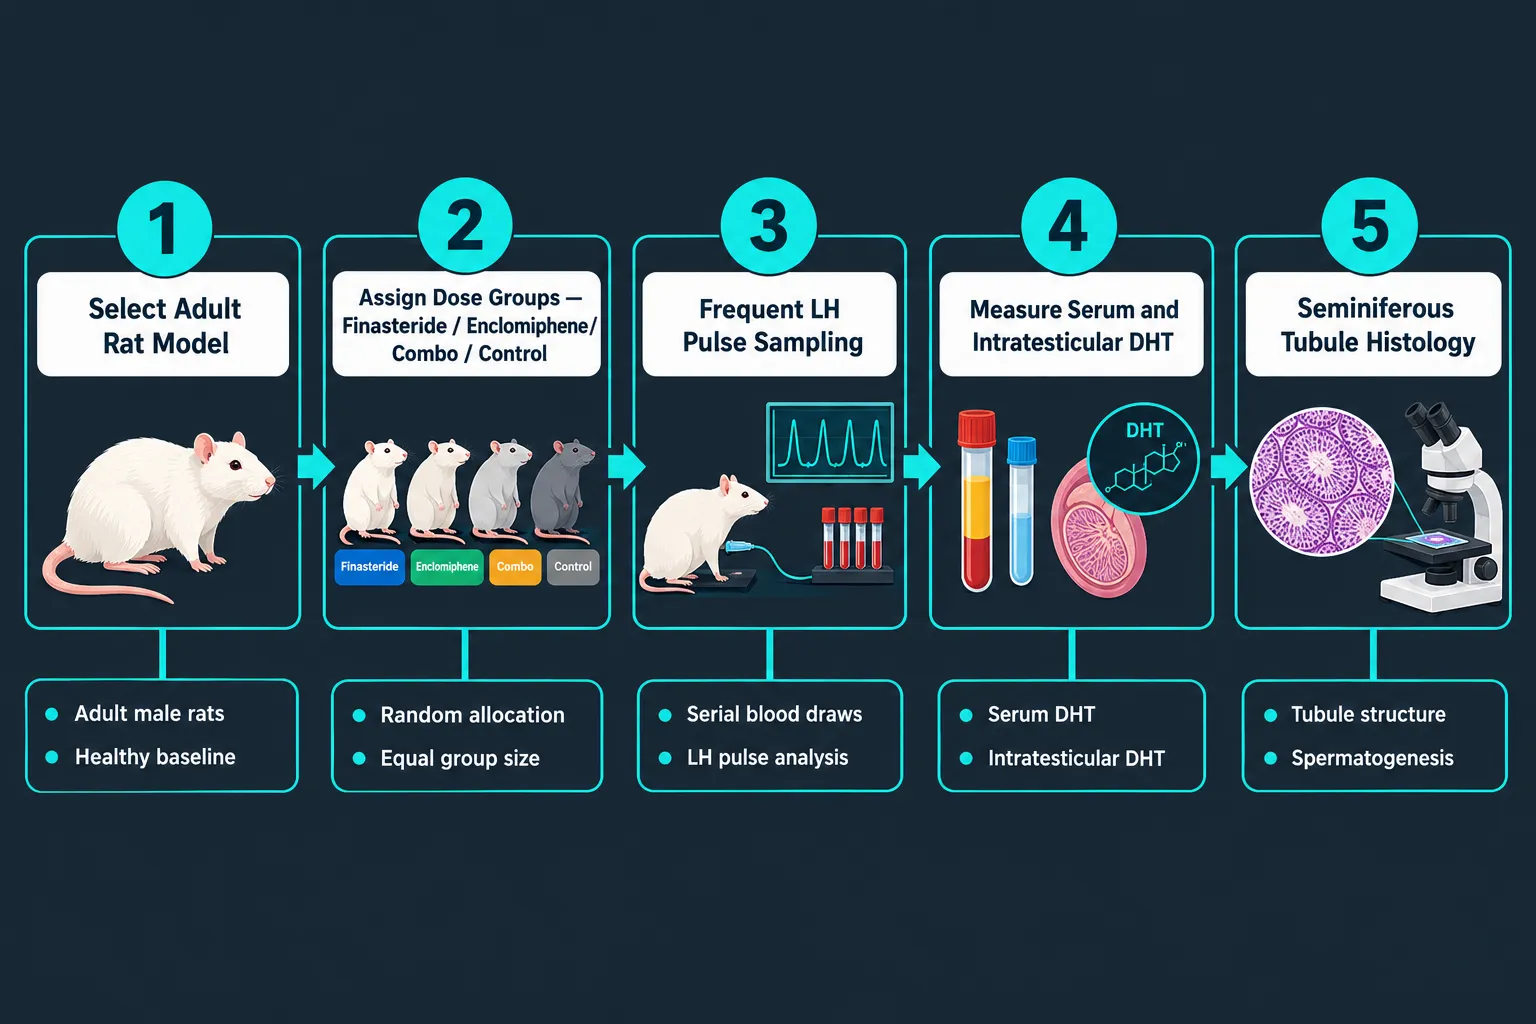
  • Rigorous future studies require adult rodent models, frequent LH pulse sampling, intratesticular hormone measurements, and histologic evaluation of seminiferous tubules.

How 5-Alpha Reductase Inhibition Disrupts Endocrine Feedback Loops
How 5-Alpha Reductase Inhibition Disrupts Endocrine Feedback Loops

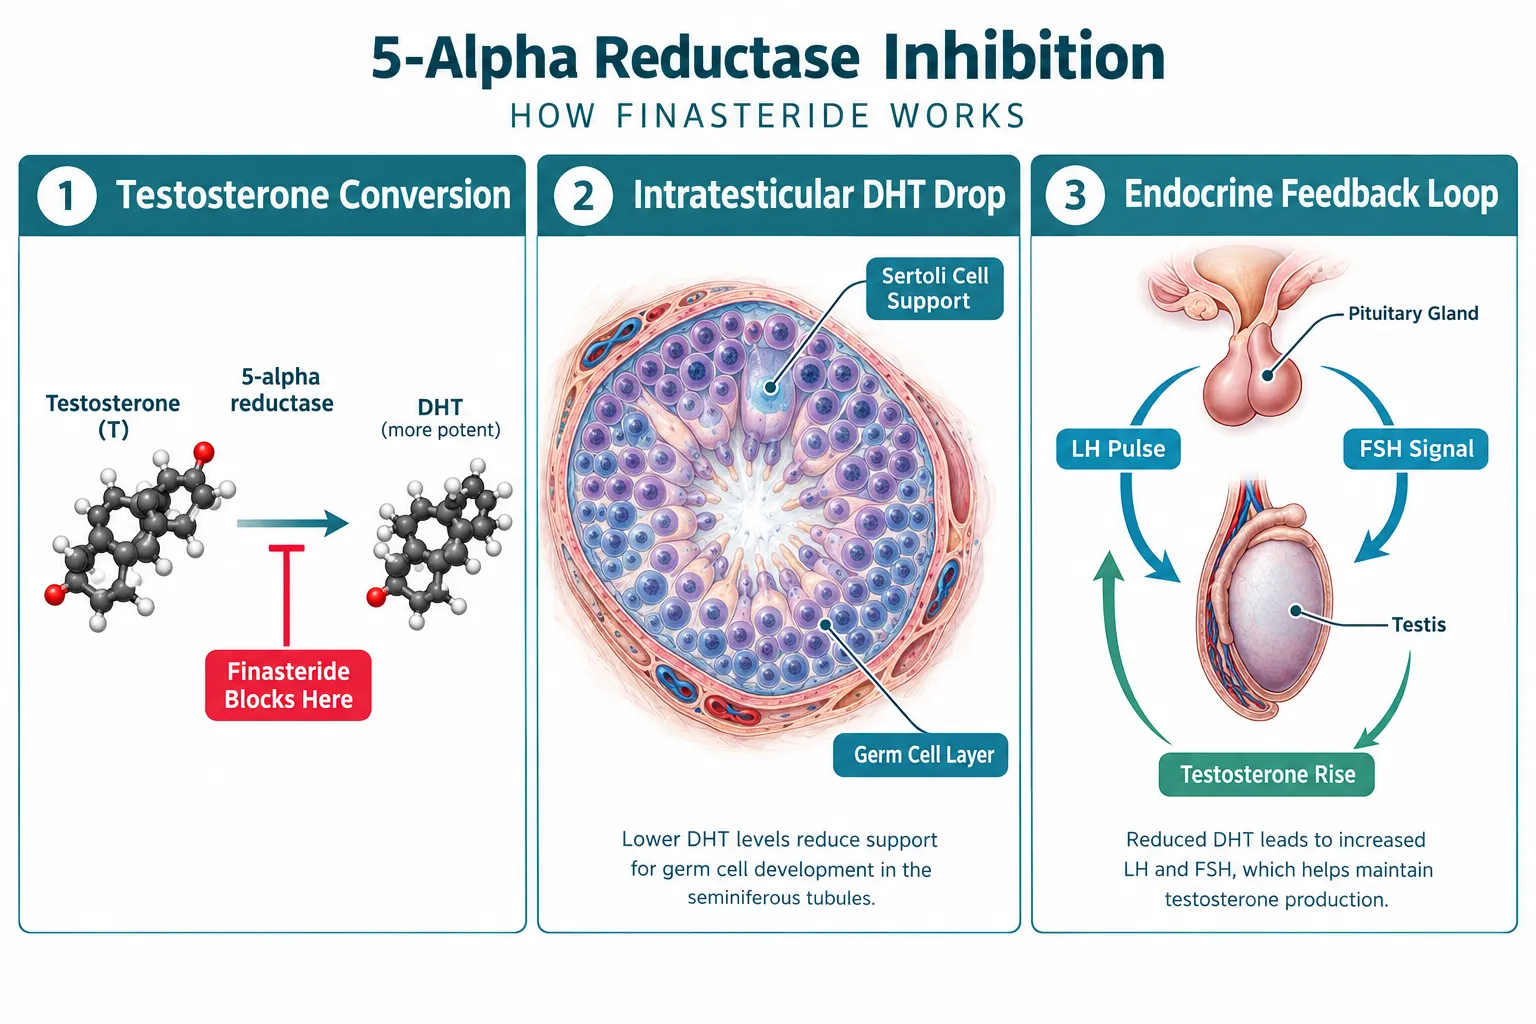
Finasteride works by blocking the enzyme 5-alpha reductase, which converts testosterone into dihydrotestosterone (DHT). In prostate and testicular tissue, DHT is a more potent androgen than testosterone. When finasteride reduces intratesticular DHT, it does not simply lower one hormone in isolation, it modifies the entire androgenic signaling environment that supports spermatogenesis.

In rat studies where 5-alpha reductase is inhibited, recovery of spermatogenesis after testosterone suppression is notably impaired. This implicates intratesticular DHT as a critical driver of normal germ cell development and tubular function, not merely a byproduct of testosterone metabolism. Rodent data also show that finasteride reduces the diameter of seminiferous and epididymal tubules in vitro, though in vivo effects are less consistent, an important distinction for study design.

At the clinical level, the dose matters. Studies using 1 mg finasteride daily found no significant changes in sperm concentration or motility in healthy adult men. Higher doses, 5 mg finasteride or combined with dutasteride, produced measurable reductions in sperm concentration and motility, with partial recovery at 12 months and full parameter restoration within six months of stopping treatment. These findings reinforce that DHT suppression along the HPG (hypothalamic-pituitary-gonadal) axis is dose-dependent and reversible, but still consequential for fertility planning.

Key point: Finasteride does not suppress LH or FSH directly. It acts downstream of gonadotropin signaling. This is why combining it with an agent that directly modulates gonadotropin output, like enclomiphene, creates a pharmacologically distinct scenario.


Enclomiphene, LH Pulsatility, and Spermatogenesis: What Rodent and Human Data Show
Enclomiphene, LH Pulsatility, and Spermatogenesis: What Rodent and Human Data Show

Enclomiphene is the trans-isomer of clomiphene citrate. Its primary mechanism involves antagonizing estrogen receptors at the pituitary, thereby reducing negative feedback and allowing LH and FSH secretion to rise. In adult men with secondary hypogonadism, clinical data confirm that enclomiphene increases LH, FSH, and total testosterone while preserving spermatogenesis, an advantage over exogenous testosterone replacement, which consistently suppresses sperm production.

A 2026 position statement from an andrology and urology society describes enclomiphene as capable of increasing total testosterone comparably to testosterone gels while maintaining or improving sperm counts. The statement calls for further mechanistic studies, specifically including detailed LH pulsatility assessment. Clinical pharmacokinetic data also show that serum enclomiphene peaks do not align precisely with LH pulses; instead, LH remains pulsatile but elevated overall. This suggests enclomiphene raises the tonic LH baseline without abolishing physiological pulse architecture.

However, immature rodent data tell a different story. In 21-day-old male rats given subcutaneous enclomiphene at 0.25-0.5 mg per animal daily for 24 days, the compound inhibited spermatogenesis and decreased serum LH and testosterone, in both intact and castrated animals. This means enclomiphene functioned as a functional anti-gonadotropic agent in immature rodents rather than a fertility-preserving serm. This species-, age-, and dose-dependent inversion is critical for any preclinical study design.

"Enclomiphene's effect on gonadotropins is not universal, adult and immature rodent models can produce opposite hormonal outcomes at comparable doses."

Researchers exploring serm-based protocols alongside other research compounds should treat this age-dependency as a primary variable in any study design. Those working with serm, ipamorelin, and CJC-1295 dosage protocols may also find that gonadotropin modulation interacts with growth hormone axis signaling in ways that complicate spermatogenic endpoints.


Evaluating Finasteride and Enclomiphene Co-Administration in Rodent Models: Research Gaps and Design Priorities
Evaluating Finasteride and Enclomiphene Co-Administration in Rodent Models: Research Gaps and Design Priorities

No existing study has placed finasteride and enclomiphene co-administration within a single controlled rodent experiment measuring DHT, LH pulsatility, and spermatogenesis together. Evaluating finasteride and enclomiphene co-administration in rodent models requires a framework that addresses each gap systematically.

Projected mechanistic interaction:

Variable Finasteride Effect Enclomiphene Effect (Adult) Combined, Predicted
Serum testosterone Slight increase (reduced DHT feedback) Significant increase High
Intratesticular DHT Decreased Indirect increase via LH Uncertain
LH pulsatility No direct change Elevated, pulsatility preserved Elevated baseline
Spermatogenesis May impair recovery Preserved or improved Unknown

The table above highlights that co-administration could produce elevated systemic testosterone alongside reduced intratesticular DHT, two outcomes working in opposite directions on sperm production. Net spermatogenic outcomes cannot be confidently predicted without direct experimental data.

Recommended study design elements:

  • Use adult (not immature) rat or mouse models to avoid the anti-gonadotropic paradox seen in juvenile rodents
  • Assign four groups: finasteride only, enclomiphene only, combination, and vehicle control
  • Collect blood samples at high frequency (every 10-15 minutes for 6 hours) to characterize LH pulse amplitude and frequency
  • Measure both serum and intratesticular testosterone and DHT separately
  • Perform histologic analysis of seminiferous tubules to distinguish germ cell stage arrest from global spermatogenic suppression

Researchers interested in how peptide compounds interact with endocrine recovery may also find it useful to review SS-31 mitochondrial dynamics research, given that mitochondrial function in Leydig and Sertoli cells can influence steroidogenesis independently of gonadotropin signaling. Similarly, cellular energy demands in spermatogenic tissue have been explored in SS-31 kidney health research, which offers methodological parallels for assessing oxidative stress in endocrine tissues.

For those comparing growth hormone secretagogue protocols and their potential crossover with reproductive endocrinology research, resources on CJC-1295 and ipamorelin cycle protocols provide relevant background on pulsatile hormone release methodology. Understanding growth hormone pulse architecture can inform LH pulse measurement design, particularly around sampling frequency and assay sensitivity.

Finally, researchers sourcing research-grade compounds for preclinical use should consult peptide supplier comparison resources to ensure compound purity and lot-to-lot consistency, both of which are critical when measuring subtle hormonal endpoints like LH pulse amplitude.


Conclusion

The intersection of 5-alpha reductase inhibition and selective estrogen receptor modulation via enclomiphene represents one of the more underexplored areas in male reproductive endocrinology research. Finasteride and enclomiphene co-administration, when evaluated for effects on DHT, LH pulsatility, and spermatogenesis in rodent models, presents a mechanistic puzzle with real translational relevance for men using finasteride who also need fertility-preserving androgen support.

Actionable next steps for researchers:

  1. Design studies exclusively with adult rodent models to avoid confounding age-dependent enclomiphene anti-gonadotropic effects.
  2. Incorporate high-frequency LH sampling protocols to capture both pulse amplitude and frequency, not just mean LH levels.
  3. Measure intratesticular DHT separately from serum DHT, these can diverge significantly under dual drug exposure.
  4. Pre-register study designs in a public registry to reduce publication bias around negative or null spermatogenic findings.
  5. Plan for a recovery arm (post-drug washout) to assess reversibility, since both finasteride and enclomiphene effects on spermatogenesis appear dose- and duration-dependent.

Until controlled rodent data exist, any clinical extrapolation of combined finasteride and enclomiphene use in fertility contexts remains speculative. The field needs well-powered, mechanistically rigorous preclinical studies before co-administration protocols can be rationally evaluated or recommended.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/finasteride-and-enclomiphene-co-administration-evaluating-dht-lh-pulsatility-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-27 13:08:192026-10-27 13:08:19Finasteride and Enclomiphene Co-Administration: Evaluating DHT, LH Pulsatility, and Spermatogenesis in Rodent Models

Tag Archive for: male fertility research

The Role of Peptides in Regulating Estrogen Receptor Activity: A Focus on Enclomiphene Research

The Role of Peptides in Regulating Estrogen Receptor Activity: A Focus on Enclomiphene Research

June 30, 2026/0 Comments/by Pure Tested

Secondary hypogonadism affects an estimated 2–4% of adult men, yet a large portion of cases remain undertreated or managed with therapies that compromise fertility. The role of peptides in regulating estrogen receptor activity: a focus on enclomiphene research offers a compelling alternative pathway — one that works with the body's own hormonal architecture rather than bypassing it.

Detailed () scientific illustration showing a cross-sectional diagram of the hypothalamic-pituitary-gonadal axis with

Key Takeaways

  • Enclomiphene is the trans-isomer of clomiphene citrate and acts as a pure estrogen receptor antagonist in the hypothalamus and pituitary.
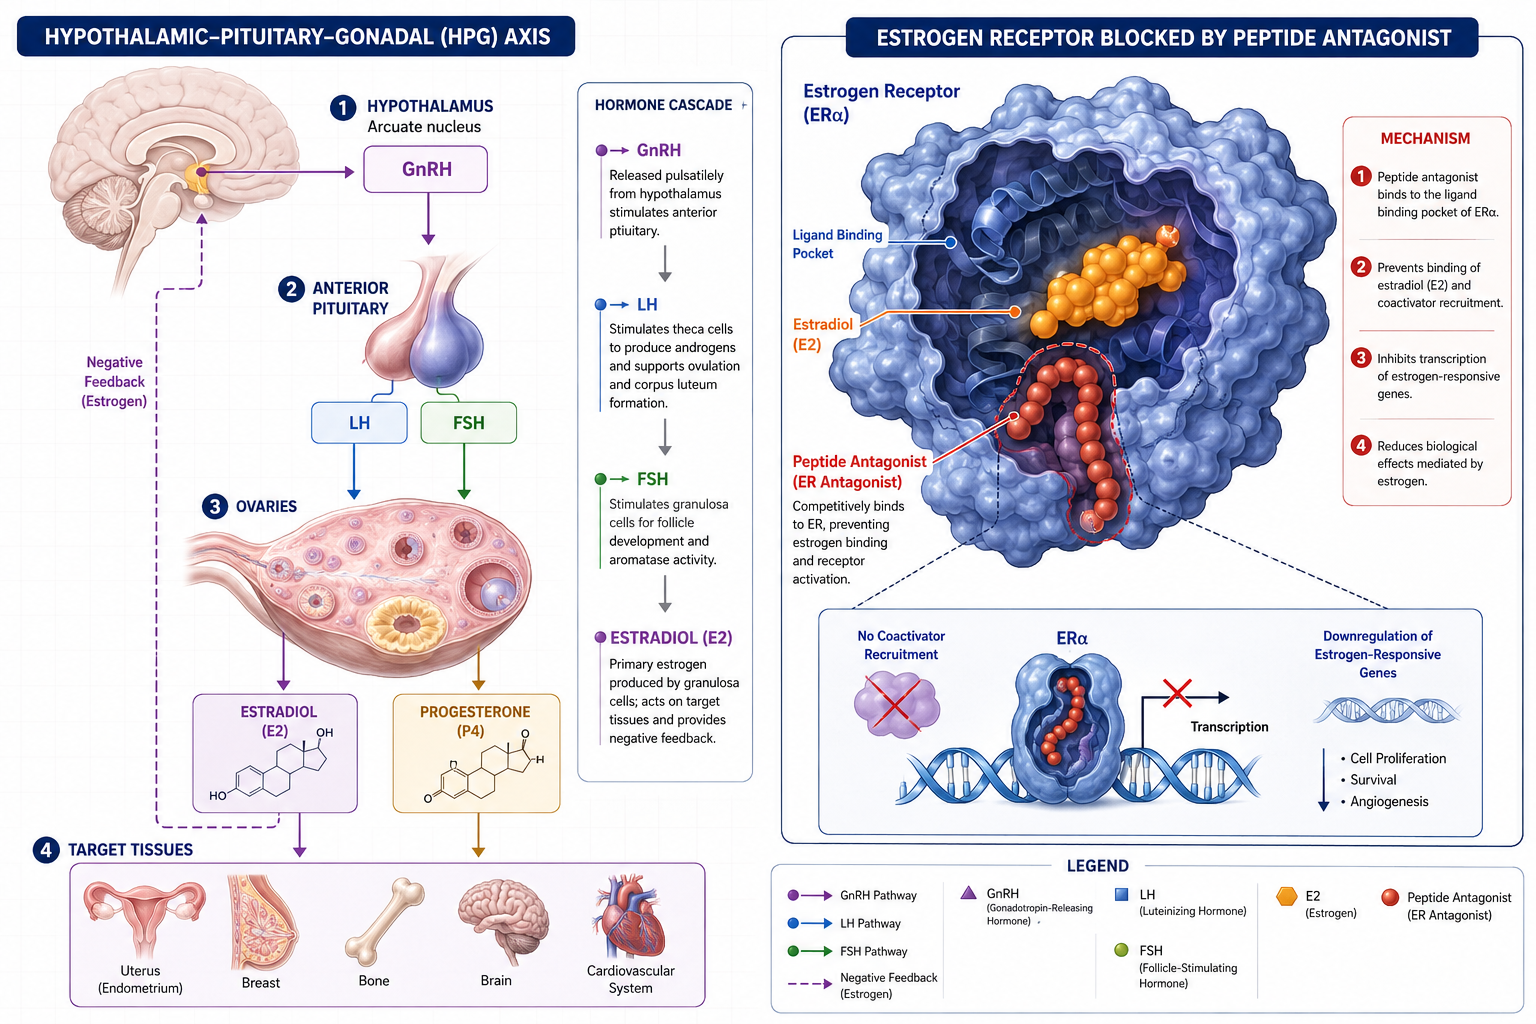
  • By blocking estradiol's negative feedback signal, enclomiphene triggers a natural cascade that raises GnRH, LH, FSH, and ultimately testosterone.
  • Unlike traditional testosterone replacement therapy (TRT), enclomiphene preserves sperm counts and testicular function.
  • Early research suggests favorable effects on fasting plasma glucose, pointing to potential metabolic benefits.
  • Enclomiphene is currently available through compounding pharmacies and is not FDA-approved as a standalone compound as of 2026.

How Enclomiphene Interacts with Estrogen Receptors

Enclomiphene belongs to a class of compounds called selective estrogen receptor modulators, or serms. Its molecular formula is C26H28ClNO, with a molecular weight of 406.0 g/mol. As the trans-isomer of clomiphene citrate, it functions as a pure estrogen receptor antagonist specifically in the hypothalamus and pituitary gland.

Here is how the mechanism unfolds:

  1. Circulating estradiol normally binds to estrogen receptors in the hypothalamus, sending a negative feedback signal that suppresses GnRH release.
  2. Enclomiphene occupies those same receptors, blocking estradiol from binding.
  3. With the negative feedback removed, the hypothalamus increases GnRH secretion.
  4. Elevated GnRH drives the pituitary to release more luteinizing hormone (LH) and follicle-stimulating hormone (FSH).
  5. Higher LH levels signal the testes to produce more endogenous testosterone.

"Enclomiphene stimulates natural testosterone production while preserving fertility — a key distinction from exogenous testosterone therapies." — Dr. Joe S. Lancaster, MD, board-certified OB-GYN and hormone specialist.

This cascade is precisely why the role of peptides in regulating estrogen receptor activity: a focus on enclomiphene research has gained traction among endocrinology researchers. Researchers exploring related peptide mechanisms, such as those studying epithalon and NAD-based hormonal pathways, have noted similar upstream signaling dynamics worth comparing.


Clinical Evidence and Comparison with Traditional TRT

Clinical Evidence and Comparison with Traditional TRT

A randomized phase II clinical trial demonstrated that enclomiphene citrate successfully raised morning serum testosterone and LH levels in men with secondary hypogonadism — results comparable to those achieved with topical testosterone gel. Critically, participants maintained normal sperm counts throughout the study period.

Enclomiphene vs. Traditional Testosterone Replacement

Parameter Enclomiphene Exogenous TRT
Endogenous testosterone Increased Suppressed
Sperm count Preserved Often reduced
Testicular function Maintained Risk of atrophy
HPG axis activity Stimulated Suppressed
Metabolic effect Favorable glucose data Variable

Traditional TRT introduces testosterone from an external source, which suppresses the hypothalamic-pituitary-gonadal (HPG) axis. This can result in testicular atrophy and oligospermia — a significant concern for men who wish to maintain fertility. Enclomiphene sidesteps this problem entirely.

Short-term safety data for enclomiphene have been satisfactory and broadly comparable to testosterone gels and placebo groups. Additionally, early data showed improved fasting plasma glucose levels, suggesting potential utility in men with secondary hypogonadism linked to obesity or metabolic syndrome.

For researchers exploring related hormonal optimization compounds, resources on MOTS-C peptide research and the IPA-Sermorelin research stack provide useful context on how peptide-based approaches can complement endocrine modulation strategies.


Dosage, Regulatory Status, and Research Outlook

Dosage, Regulatory Status, and Research Outlook

The standard oral dosage studied in research protocols ranges from 12.5 to 25 mg per day. Enclomiphene's half-life of approximately 10 hours supports once-daily dosing, making it practically convenient for research administration.

As of 2026, enclomiphene is not FDA-approved as a standalone drug. It remains accessible through compounding pharmacies. Clomiphene citrate — which contains both the enclomiphene (trans) and zuclomiphene (cis) isomers — holds FDA approval for female ovulatory dysfunction.

Ongoing research is investigating enclomiphene's potential across several areas:

  • Secondary hypogonadism associated with obesity
  • Metabolic syndrome management in men
  • Male infertility where HPG axis preservation is essential

Researchers interested in the broader landscape of serm-adjacent compounds can review the serm 10mg product research page for additional context. Those exploring recovery-oriented peptides may also find value in reviewing top healing peptides and their mechanisms as complementary reading.

For quality benchmarking in peptide research, understanding Bachem reference standards and peptide benchmarks is essential when evaluating compound purity and study reliability.


Conclusion

The role of peptides in regulating estrogen receptor activity: a focus on enclomiphene research represents one of the more nuanced intersections of endocrinology and peptide science available for study in 2026. Enclomiphene's ability to block estrogen receptor activity at the hypothalamic-pituitary level — triggering a natural hormonal cascade without suppressing the HPG axis — sets it apart from conventional testosterone replacement approaches.

Actionable next steps for researchers:

  • Review phase II clinical trial data on enclomiphene citrate and secondary hypogonadism before designing new protocols.
  • Compare enclomiphene's receptor-binding profile against other serms when assessing research scope.
  • Consult compounding pharmacy documentation and current regulatory guidance before sourcing.
  • Explore synergistic peptide research areas, including metabolic and recovery pathways, to build a more complete endocrine research framework.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/The-Role-of-Peptides-in-Regulating-Estrogen-Receptor-Activity-A-Focus-on-Enclomiphene-Research.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-30 13:04:582026-07-20 15:01:53The Role of Peptides in Regulating Estrogen Receptor Activity: A Focus on Enclomiphene Research
Enclomiphene vs. Tamoxifen: Comparative Research on serm Peptide Receptor Modulation

Enclomiphene vs. Tamoxifen: Comparative Research on serm Peptide Receptor Modulation

June 22, 2026/0 Comments/by Pure Tested

Only one of these two compounds preserves male fertility while raising testosterone — and the distinction comes down to how each molecule interacts with estrogen receptors at the cellular level. The field of Enclomiphene vs. Tamoxifen: Comparative Research on serm Peptide Receptor Modulation has grown substantially as researchers seek more targeted hormonal interventions that avoid the reproductive suppression caused by conventional testosterone replacement therapy.

Both enclomiphene and tamoxifen belong to the Selective Estrogen Receptor Modulator (serm) class, yet their pharmacological profiles, half-lives, and clinical applications differ in ways that matter deeply for research design and therapeutic strategy.


Key Takeaways

  • Enclomiphene is the trans-isomer of clomiphene citrate and acts as a pure estrogen receptor antagonist in the hypothalamus and pituitary, stimulating endogenous testosterone production.
  • Tamoxifen has a significantly longer half-life (5-7 days) compared to enclomiphene (approximately 10 hours), affecting how quickly dosing adjustments take effect.
  • Enclomiphene shows a cleaner side-effect profile than clomiphene citrate because it lacks the zuclomiphene (cis-isomer) component associated with visual disturbances and mood changes.
  • Tamoxifen remains the preferred serm for gynecomastia management due to its potent antagonism at breast tissue estrogen receptors.
  • Neither compound has received FDA approval as a standalone male hypogonadism treatment as of 2026, though both are used off-label in clinical and research contexts.

Key Takeaways

Mechanisms of Action: How Each serm Engages Estrogen Receptors

Understanding Enclomiphene vs. Tamoxifen: Comparative Research on serm Peptide Receptor Modulation begins at the receptor level. Both compounds bind estrogen receptors but do so in different tissues with different downstream effects.

Enclomiphene is the trans-isomer of clomiphene citrate. It acts as an estrogen receptor antagonist specifically in the hypothalamus and pituitary gland. By blocking estrogen's negative feedback signal at these sites, enclomiphene triggers increased secretion of:

  • Gonadotropin-releasing hormone (GnRH)
  • Luteinizing hormone (LH)
  • Follicle-stimulating hormone (FSH)

This cascade stimulates the testes to produce testosterone endogenously, preserving the hypothalamic-pituitary-testicular (HPT) axis rather than bypassing it.

Tamoxifen operates through a similar upstream mechanism but was originally developed for breast cancer treatment. It competitively blocks estrogen receptors in breast tissue and, when used in male health contexts, also reduces pituitary estrogen feedback — raising LH and FSH levels and, consequently, testosterone output.

"The key distinction is tissue selectivity: enclomiphene's activity is concentrated at the hypothalamic-pituitary axis, while tamoxifen's receptor modulation extends to peripheral tissues including breast, bone, and liver."

For researchers exploring broader receptor modulation frameworks, metabolic modulation research lines provide useful context on how peptide-receptor interactions extend beyond hormonal axes.


Mechanisms of Action: How Each serm Engages Estrogen Receptors

Pharmacokinetics and Clinical Profiles Compared

The pharmacokinetic differences between these two serms are significant for research protocol design.

Parameter Enclomiphene Tamoxifen
Half-life ~10 hours 5-7 days
Active metabolites Minimal Yes (endoxifen)
Dosing frequency Daily (12.5-25 mg) Daily or less frequent
FDA approval (male use) Not approved (2026) Not approved (male use)
Primary research use Secondary hypogonadism Gynecomastia, hypogonadism

Enclomiphene's shorter half-life allows researchers and clinicians to make faster dosing adjustments. Tamoxifen's longer half-life and active metabolite (endoxifen) mean that steady-state concentrations take longer to establish and dissipate.

Side-effect profiles also diverge meaningfully:

  • Enclomiphene: transient headaches, hot flashes; notably absent are the visual disturbances linked to zuclomiphene in standard clomiphene citrate
  • Tamoxifen: risk of thromboembolic events, mood changes, and potential hepatotoxicity with long-term use

Both compounds maintain or enhance spermatogenesis, which gives them a clear advantage over exogenous testosterone therapy for fertility-conscious research subjects. For comparison with other peptide compounds studied in neuroendocrine contexts, neuroendocrine and innate immunity research offers relevant background.

Those researching serm compounds for laboratory use can review the serm 10mg research product for sourcing reference.


Pharmacokinetics and Clinical Profiles Compared

Research Applications and Comparative Utility in 2026

The comparative analysis of Enclomiphene vs. Tamoxifen: Comparative Research on serm Peptide Receptor Modulation reveals distinct niches for each compound in active research programs.

Enclomiphene has completed Phase III clinical trials demonstrating statistically significant increases in testosterone levels alongside preserved spermatogenesis. Researchers studying secondary hypogonadism in younger males favor enclomiphene because it stimulates the natural HPT axis without suppressing it. Its cleaner isomer profile reduces confounding variables in study design.

Tamoxifen remains the more established compound for gynecomastia management research, given its potent and well-documented antagonism at breast tissue estrogen receptors. Its longer half-life also makes it useful in protocols where less frequent dosing is preferred.

Both serms are being examined alongside peptide-based interventions. Researchers comparing hormonal optimization strategies often cross-reference findings with growth hormone secretagogue research, such as ipamorelin vs. tesa comparisons and tesa mechanism and application data, since both categories affect body composition and metabolic signaling.

For researchers interested in longevity and cellular signaling intersections, the Glow Blend longevity research themes and Epithalon vs. NAD evidence pages provide complementary reading on receptor-level interventions.


Conclusion

The comparative research on Enclomiphene vs. Tamoxifen: Comparative Research on serm Peptide Receptor Modulation makes clear that these are not interchangeable compounds. Enclomiphene offers a more targeted hypothalamic-pituitary mechanism, a shorter half-life for flexible dosing, and a favorable side-effect profile — making it the stronger candidate for secondary hypogonadism and fertility-preservation research. Tamoxifen retains its edge in gynecomastia management and longer-duration protocols.

Actionable next steps for researchers:

  1. Define the target tissue and hormonal axis before selecting a serm for a given protocol.
  2. Account for half-life differences when designing washout periods and dosing schedules.
  3. Cross-reference serm data with peptide-based hormonal research to build a more complete picture of receptor modulation strategies.
  4. Monitor regulatory updates, as neither compound holds FDA approval for male hypogonadism treatment as of 2026.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Enclomiphene-vs.-Tamoxifen-Comparative-Research-on-serm-Peptide-Receptor-Modulation.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-22 13:03:462026-07-20 15:02:34Enclomiphene vs. Tamoxifen: Comparative Research on serm Peptide Receptor Modulation
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top