Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: peptide hormones

Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies

Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies

September 8, 2026/0 Comments/in Uncategorized/by

Fewer than one in five researchers working with hormone-modulating peptides routinely track prostate-specific antigen as a safety endpoint, yet the field of prostate specific antigen and peptide hormones is rapidly reshaping how enclomiphene and GLP-class research studies are designed, monitored, and interpreted. Understanding the intersection of PSA biology with emerging serm and incretin-based research is no longer optional for anyone serious about endocrine safety endpoints.

Key Takeaways

  • PSA is a serine protease produced in prostate tissue and regulated by androgen signaling, making it a logical safety marker in any research protocol that modulates testosterone or related hormones.
  • Enclomiphene studies show small, clinically minor PSA increases compared with testosterone-replacement protocols, but baseline and periodic PSA monitoring remains standard practice.
  • GLP-1 receptor agonist research uses PSA primarily for risk stratification rather than as a direct drug-response marker.
  • Mechanistic data suggest GLP-1 receptor activation may suppress oncogenic signaling in prostate tissue, giving PSA a secondary role as an indirect safety endpoint.
  • Unified PSA monitoring thresholds for enclomiphene and GLP-class research are expected to converge by 2030.

What PSA Is and Why It Matters in Peptide Hormone Research
What PSA Is and Why It Matters in Peptide Hormone Research

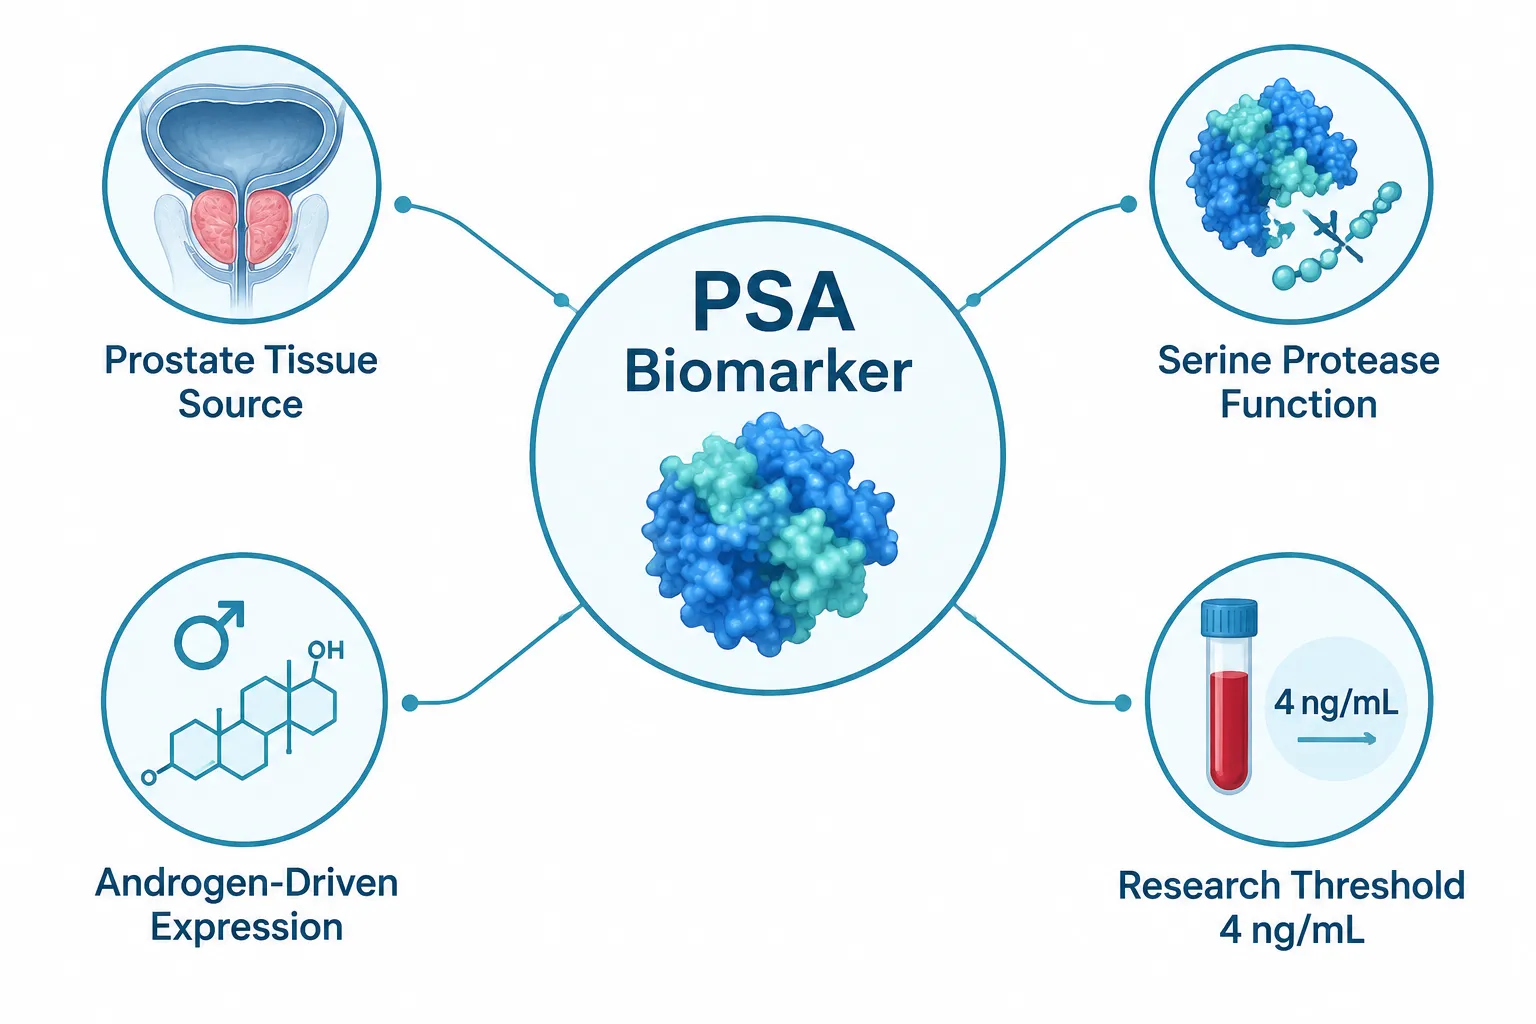
Prostate-specific antigen is a serine protease enzyme encoded by the KLK3 gene and secreted almost exclusively by prostate epithelial cells. Its primary physiological role is to liquefy seminal fluid, but because its expression is tightly driven by androgen receptor signaling, serum PSA levels rise and fall in response to changes in the androgen environment.

This androgen-sensitivity is precisely what makes PSA relevant to peptides and polypeptides in endocrine pharmacology. Any compound that raises circulating testosterone, whether a peptide hormone, a serm like enclomiphene, or an exogenous androgen, can theoretically stimulate PSA production. Conversely, compounds that blunt androgen signaling tend to suppress PSA.

Standard PSA thresholds used in research monitoring:

PSA Level (ng/mL) Interpretation in Research Context
Below 1.0 Low baseline; minimal androgen stimulation
1.0-4.0 Normal range; monitor for velocity changes
Above 4.0 Referral threshold; warrants further evaluation
Velocity > 0.75/year Clinically significant rise regardless of absolute value

For researchers working with peptides in basic cell biology and hormone analogues, PSA provides a low-cost, widely available window into androgen-axis activity that complements more expensive genomic or imaging endpoints.

Prostate Specific Antigen and Peptide Hormones in Enclomiphene Monitoring Protocols
Prostate Specific Antigen and Peptide Hormones in Enclomiphene Monitoring Protocols

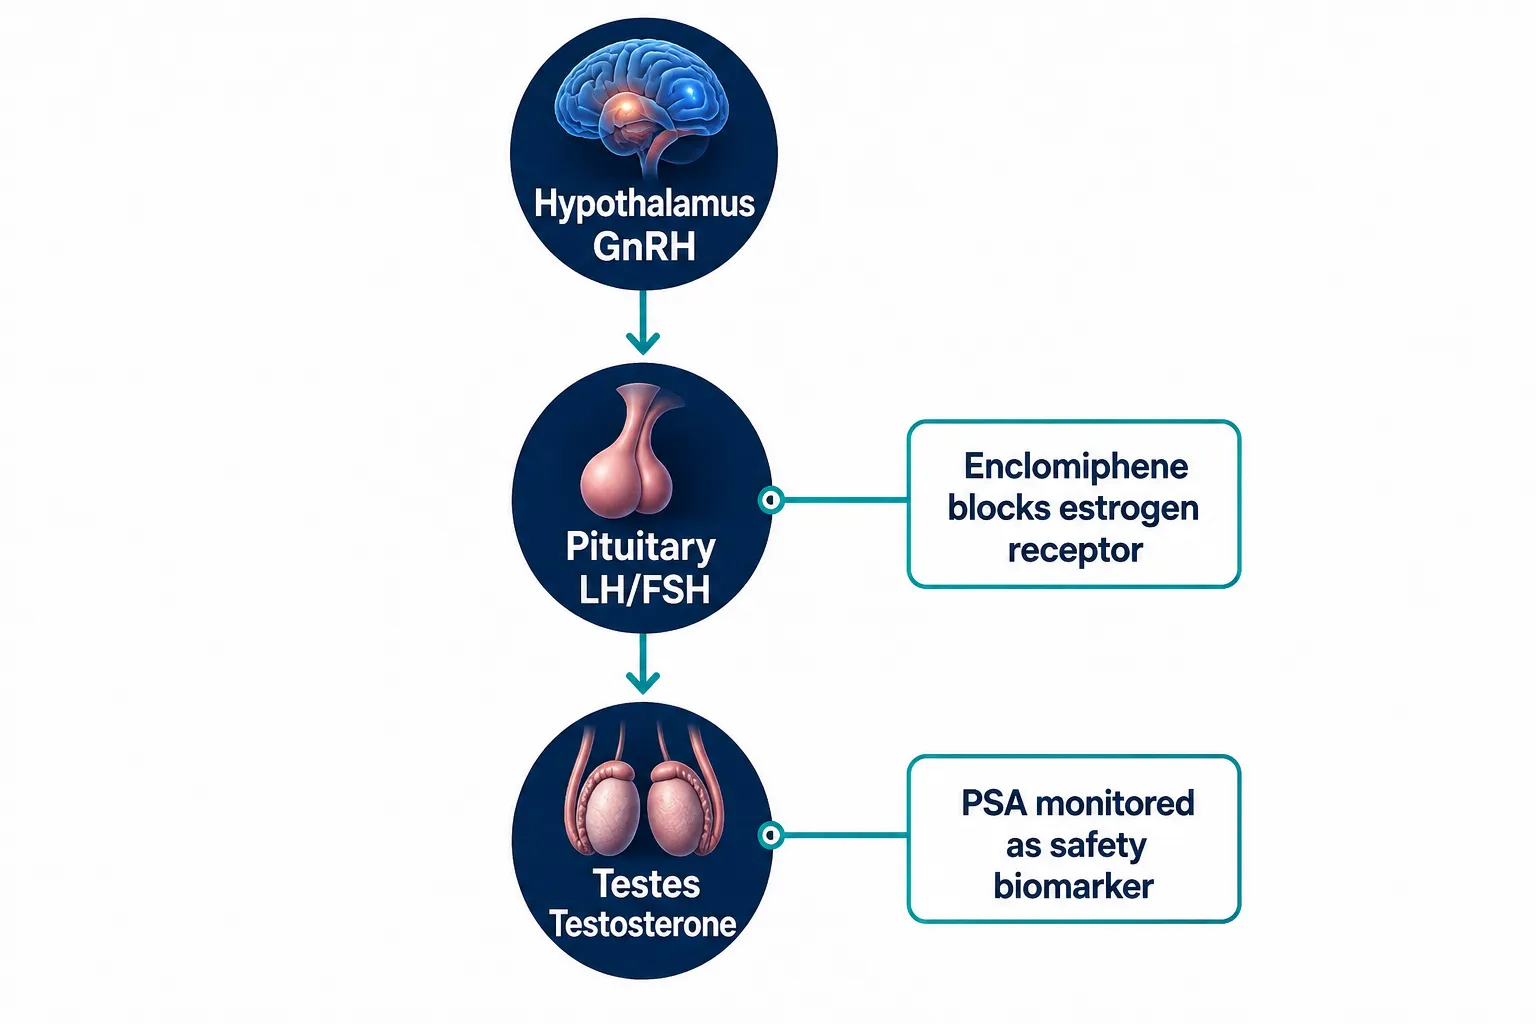
Enclomiphene citrate is the trans-isomer of clomiphene and acts as a selective estrogen receptor modulator (serm) at the hypothalamic-pituitary axis. By blocking estrogen's negative feedback, it drives a rise in LH and FSH, which in turn stimulates endogenous testosterone production. Because testosterone is the primary driver of PSA expression, any enclomiphene-mediated testosterone increase carries at least a theoretical PSA signal.

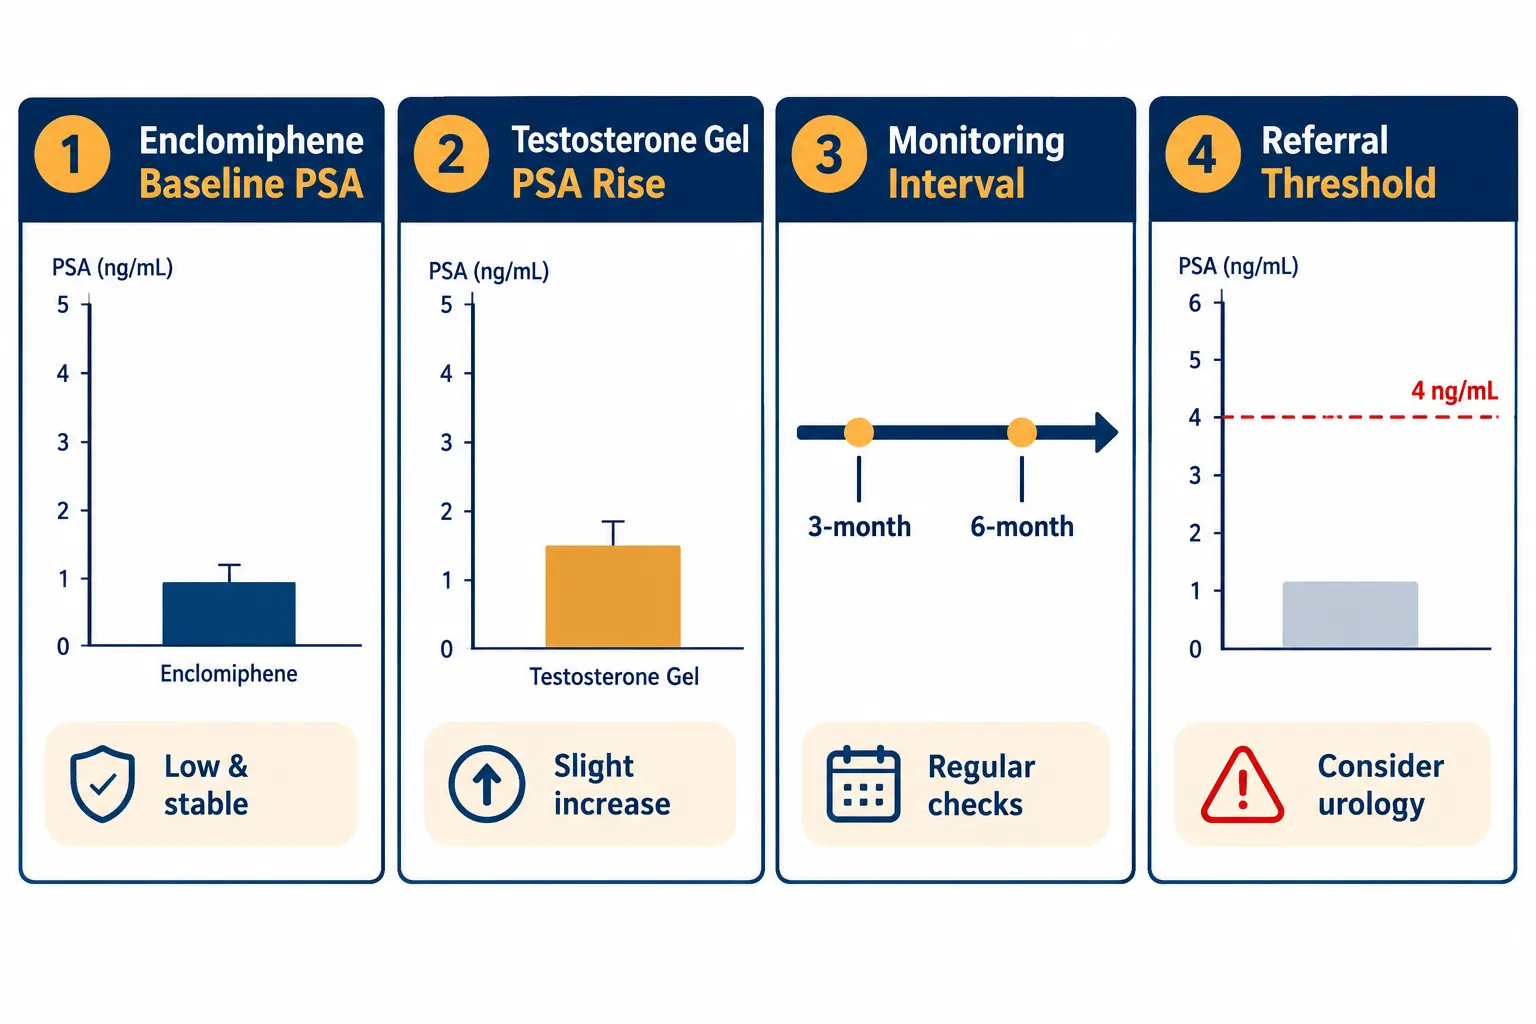
Research published through 2025 and reviewed in 2026 consistently shows that enclomiphene produces small but measurable PSA increases, typically within the normal reference range and substantially lower than the rises observed with exogenous testosterone gels or injections. Over follow-up periods extending to three years, no significant PSA impact has been confirmed, though researchers and clinicians continue to advise monitoring because the androgen-axis stimulation is real.

Current enclomiphene PSA monitoring protocol (adapted from testosterone-therapy guidelines):

  1. Establish a baseline PSA before the study compound is introduced.
  2. Repeat PSA at 3 months and 6 months after initiation.
  3. Apply the same 4 ng/mL referral threshold and 0.75 ng/mL/year velocity rule used in testosterone-replacement research.
  4. Document any concurrent medications that could confound PSA (e.g., 5-alpha reductase inhibitors).

The borrowing of thresholds from testosterone-replacement guidelines reflects a practical reality: enclomiphene-specific PSA criteria do not yet exist. Debate continues in the literature about whether early routine PSA checks add meaningful safety data in younger, otherwise healthy research subjects, but baseline and periodic monitoring remain the consensus standard.

"The PSA changes seen with enclomiphene are minor relative to exogenous testosterone, but the absence of dedicated long-term data makes monitoring a non-negotiable safety step in responsible research design."

For a broader view of how enclomiphene fits within receptor biology, the article on enclomiphene and estrogen receptor biology provides useful mechanistic context.

GLP-Class Research Studies and the Role of PSA Risk Stratification
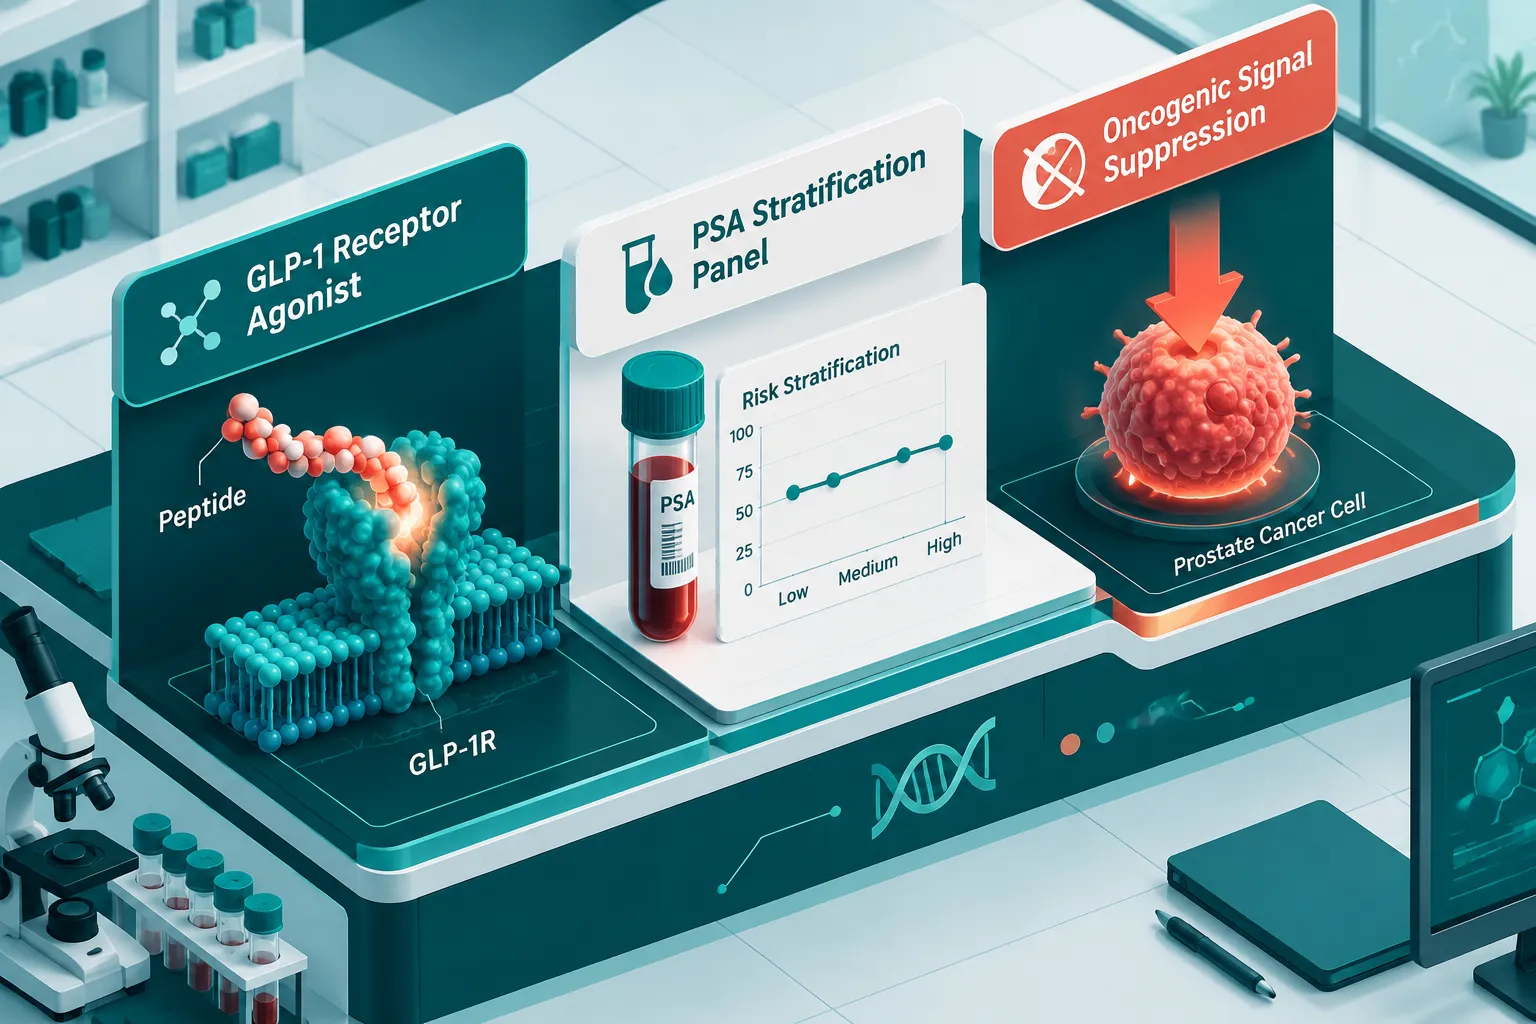
GLP-Class Research Studies and the Role of PSA Risk Stratification

The relationship between prostate specific antigen and peptide hormones in GLP-class research is fundamentally different from the enclomiphene context. GLP-1 receptor agonists, including the triple-agonist retatrutide studied in GLP-3 retatrutide phase 3 trials, do not directly stimulate androgen production. Instead, PSA enters GLP-class research as a risk stratification tool and a secondary safety endpoint.

Large-cohort analyses of GLP-1 receptor agonist users show a neutral to mildly protective prostate-cancer risk profile. Mechanistic studies add an important layer: GLP-1 receptor activation appears to suppress oncogenic signaling pathways in prostate cancer cell lines, suggesting a potential indirect protective effect. PSA is the practical instrument through which researchers detect any meaningful change in prostate cancer risk during these studies.

How PSA functions in GLP-class study designs:

  • Baseline stratification: Subjects with elevated baseline PSA are flagged for exclusion or sub-group analysis to prevent confounding.
  • Case detection: Any PSA rise during a GLP-1 study triggers standard urological workup, separating drug-related from incidental findings.
  • Cardiometabolic integration: PSA is increasingly analyzed alongside insulin resistance markers, visceral fat measurements, and inflammatory biomarkers in risk-reduction models.

This integrated approach is consistent with how carbohydrate antigens and peptide-based assays are being combined with modern research peptide endpoints to build richer safety profiles.

Researchers interested in the metabolic dimensions of GLP-class compounds can also explore tesofensine and metabolic research for a comparative look at how different appetite-modulating agents handle overlapping endpoints.

Where Enclomiphene and GLP-Class PSA Monitoring Are Headed

The convergence of prostate specific antigen and peptide hormones research across serm and incretin platforms is generating pressure for unified monitoring guidelines. Expert commentary in 2026 points toward a likely consensus by 2030 in which:

  • Formal PSA monitoring thresholds specific to enclomiphene will be established, rather than borrowed from testosterone-therapy protocols.
  • PSA dynamics will be incorporated as pre-specified secondary endpoints in GLP-1 and GLP-3 interventional trials, particularly those targeting obesity-related prostate cancer risk.
  • Composite biomarker panels, combining PSA with sex hormone-binding globulin, estradiol, and metabolic markers, will replace single-marker monitoring in advanced study designs.

Understanding how researchers classify hormone analogues and peptide chains is foundational to interpreting these evolving protocols. The overview at peptides in modern research covers the structural and mechanistic distinctions that underpin these monitoring decisions.

Conclusion

The intersection of prostate specific antigen and peptide hormones is no longer a niche concern. For enclomiphene research, PSA monitoring is a borrowed but essential safety practice, one that will likely gain its own dedicated thresholds as long-term data mature. For GLP-class studies, PSA serves a distinct role as a risk stratification and case-detection tool, with emerging mechanistic evidence suggesting these compounds may actually reduce prostate oncogenic signaling.

Actionable next steps for researchers:

  • Establish a documented PSA baseline before initiating any enclomiphene or testosterone-modulating protocol.
  • Apply the 4 ng/mL threshold and 0.75 ng/mL/year velocity rule as interim standards until enclomiphene-specific guidelines are published.
  • In GLP-class study designs, include PSA as a pre-specified secondary safety endpoint with a clear exclusion and referral algorithm.
  • Monitor the literature through 2026-2030 for convergence on unified PSA thresholds across serm and incretin research platforms.
  • Cross-reference PSA data with cardiometabolic and hormonal markers to build more complete safety profiles.

Staying current with these developments positions any research program to meet the higher safety and reporting standards that regulators and peer reviewers will increasingly expect.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-and-peptide-hormones-how-psa-is-used-to-monitor-enclom.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-08 13:08:202026-09-08 13:08:20Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies
Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies

Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies

September 5, 2026/0 Comments/in Uncategorized/by

More than 40 million PSA tests are ordered in the United States each year, making prostate-specific antigen one of the most tracked biomarkers in modern medicine. Yet PSA does not exist in isolation. Increasingly, research programs studying Prostate Specific Antigen, Enclomiphene, and Peptide Hormones are weaving this marker into broader hormone study frameworks, frameworks that now include selective estrogen receptor modulators (serms) like enclomiphene and peptide-based agents in the GLP class. Understanding how labs design these studies reveals why PSA belongs in the same safety panel as testosterone, LH, FSH, and pharmacokinetic peptide data.

Key Takeaways

  • PSA serves as a critical safety biomarker in male hormone studies, including serm trials involving enclomiphene citrate.
  • Enclomiphene raises testosterone while preserving sperm production, distinguishing it from testosterone replacement therapy.
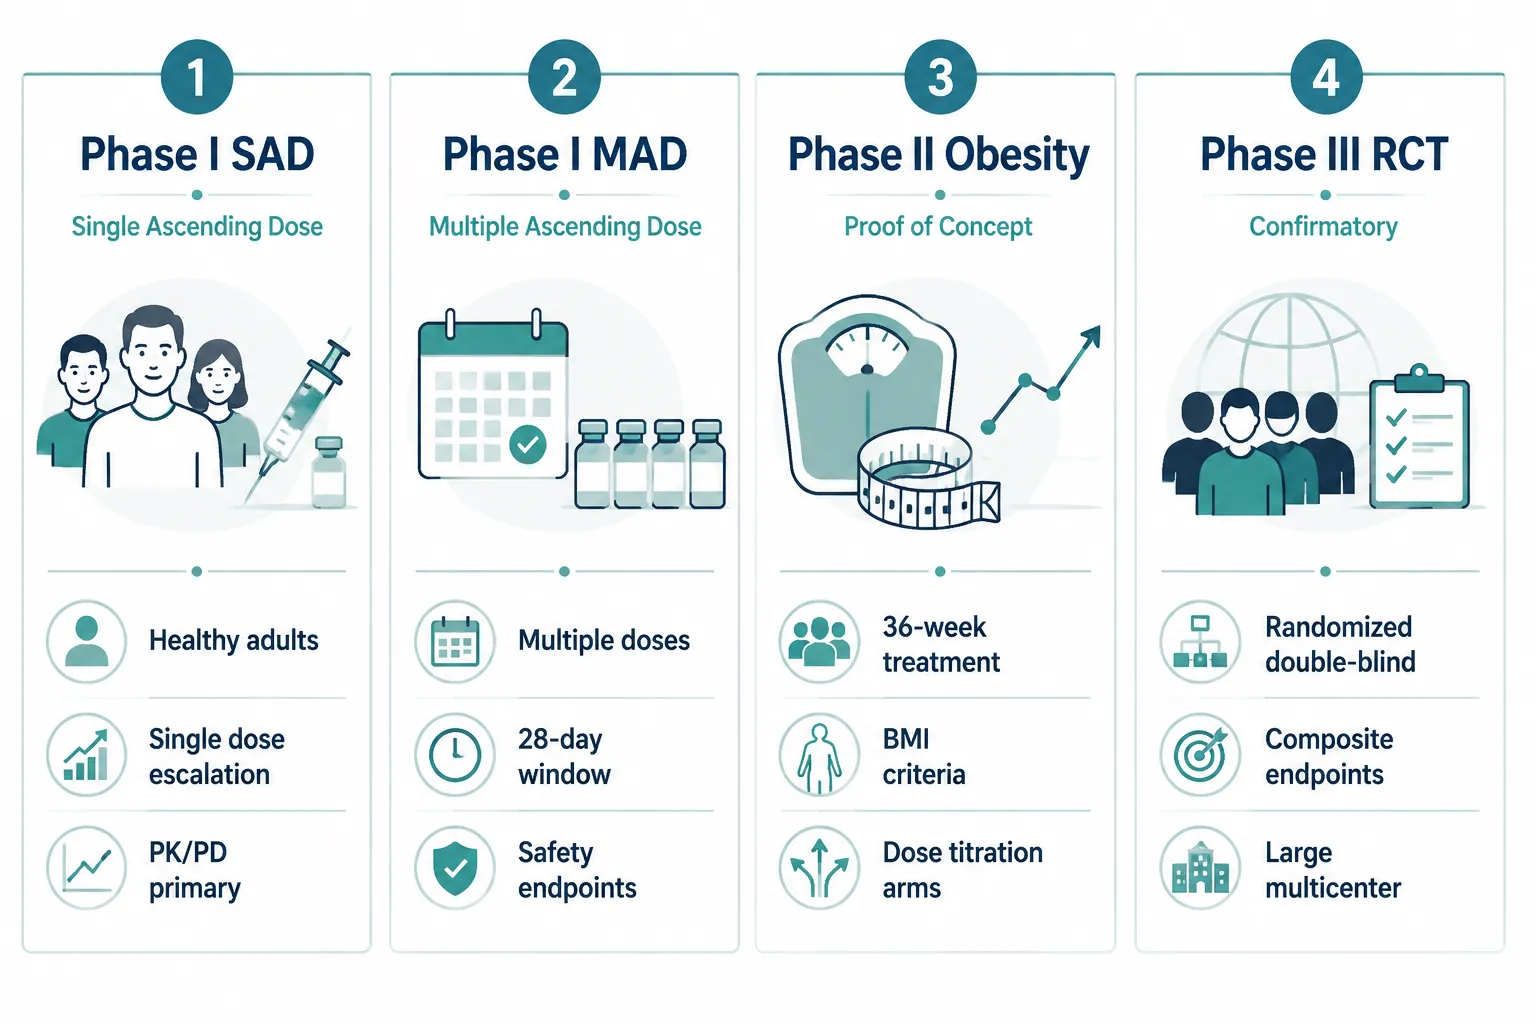
  • GLP-1 receptor agonist trials use ascending-dose, randomized, double-blind designs with composite endpoints.
  • Labs increasingly combine PSA monitoring with peptide pharmacokinetic data to build complete hormonal safety profiles.
  • Regulatory complexity, such as enclomiphene's relationship to clomiphene, directly shapes how study protocols are written.

PSA as a Biomarker in Hormone Research

PSA as a Biomarker in Hormone Research

PSA is a glycoprotein produced by prostate epithelial cells, and its serum level rises when androgen signaling increases. That biological fact makes it indispensable in any study that deliberately elevates testosterone. When a lab designs a serm trial for secondary hypogonadism, the protocol must account for the downstream androgenic effect on prostate tissue, and PSA is the most practical, non-invasive way to do that.

In enclomiphene phase III safety work, clinical laboratory tests form a core safety endpoint alongside physical exams, visual acuity checks, and slit-lamp eye examinations. Although published summaries do not always headline PSA explicitly, practitioners running off-label hormone protocols consistently include it in serial safety panels. The reasoning is straightforward: if enclomiphene successfully raises morning total testosterone from below 300 ng/dL into the normal range, prostate tissue will experience that androgen signal. Monitoring PSA at baseline, mid-study, and endpoint catches any clinically meaningful rise before it becomes a safety event.

Why PSA matters beyond prostate cancer screening:

  • It quantifies androgenic stimulation of prostate tissue in real time.
  • It provides a continuous safety variable rather than a binary pass/fail outcome.
  • It allows dose-adjustment decisions during titration phases.
  • It satisfies FDA expectations for safety data in androgen-modulating drug applications.

For researchers exploring therapeutic peptides alongside serms, PSA anchors the hormone safety panel to a well-validated clinical standard.

How Enclomiphene serm Studies Are Structured

The design of enclomiphene trials illustrates how Prostate Specific Antigen, Enclomiphene, and Peptide Hormones research frameworks are built from the ground up. Enclomiphene citrate is the trans-isomer of clomiphene, and its regulatory path has been complicated precisely because the FDA must decide how to treat the relationship between an isomer and an already-marketed parent compound. As of 2026, an NDA remains in progress with outstanding FDA questions on that relationship.

Phase III enclomiphene trials enrolled men aged 18-65 with secondary hypogonadism, defined as morning total testosterone below 300 ng/dL on two separate occasions with non-elevated LH. The open-label, escalating-dose design started participants at 12.5 mg with titration to 25 mg if needed over six months. The key clinical finding: enclomiphene raises total testosterone into the normal range while preserving LH, FSH, and sperm production, a meaningful advantage over exogenous testosterone replacement, which suppresses the hypothalamic-pituitary-gonadal axis.

"Enclomiphene's ability to maintain spermatogenesis while restoring testosterone makes it a structurally different intervention than TRT, and that difference demands a different safety monitoring strategy."

For more on how serm compounds are categorized and studied, researchers can explore current literature on receptor-selective mechanisms.

Standard safety panel in enclomiphene studies:

Endpoint Category Specific Measures
Androgenic safety PSA, hematocrit, lipid panel
Reproductive hormones Total testosterone, LH, FSH
Ocular safety Visual acuity, slit-lamp exam
General clinical labs CMP, CBC, adverse event log

GLP-Class Peptide Hormone Study Design

GLP-Class Peptide Hormone Study Design

The design logic for GLP-1 receptor agonist studies shares structural DNA with serm trials but diverges sharply in endpoint architecture. A first-in-human phase I study of a novel oral small-molecule GLP-1 receptor agonist illustrates the current template: three sequential parts covering single ascending dose (2.5-50 mg in healthy adults), a 28-day multiple ascending dose in healthy adults, and a 28-day weekly-titration multiple ascending dose in overweight or obese adults. All three parts are randomized, double-blind, and placebo-controlled, with safety and tolerability as primary endpoints and pharmacokinetics and pharmacodynamics as key secondary measures.

When labs repurpose existing GLP-1 agents for new indications, such as substance use disorders or neurodegenerative disease, a common design strategy emerges: keep established metabolic dosing (for example, semaglutide up to 1.0 mg once weekly) and concentrate design innovation on endpoints and patient populations. This approach reduces regulatory uncertainty because pharmacokinetic data already exists.

Researchers interested in signaling peptides and their receptor interactions will recognize that GLP-1 receptor agonists operate through similar second-messenger cascades as other peptide classes, making cross-class study design comparisons genuinely useful.

Key GLP-1 trial design principles in 2026:

  • Integrated cardiometabolic endpoints (cardiovascular events, kidney disease, weight)
  • "Low and slow" titration strategies to balance tolerability with efficacy
  • Real-world data sets used to power sample sizes and set event rate assumptions
  • Bridging studies that connect known pharmacology to new therapeutic uses

For context on how stacking or combining peptide agents affects study design, the discussion of single peptide vs stack approaches is directly relevant to multi-arm GLP-1 trial architectures.

Integrating PSA, serm, and Peptide Data Into a Unified Safety Framework

Integrating PSA, serm, and Peptide Data Into a Unified Safety Framework

The convergence of Prostate Specific Antigen, Enclomiphene, and Peptide Hormones research into unified safety frameworks reflects a broader shift in how hormone studies are powered and monitored. Labs running combination protocols, for instance, pairing a serm with a growth hormone-releasing peptide, must build safety panels that capture both androgenic effects (PSA, hematocrit) and peptide-specific effects (IGF-1, fasting glucose, injection-site reactions).

Research on Sermorelin, Ipamorelin, and CJC-1295 dosage demonstrates how multi-peptide protocols require layered monitoring, just as multi-arm GLP-1 trials require composite endpoint tracking. Similarly, Tesamorelin vs Sermorelin comparisons highlight how small structural differences between peptide agents can produce meaningfully different safety profiles, a lesson directly applicable to enclomiphene's isomeric relationship to clomiphene.

Labs designing these studies in 2026 are also increasingly using next-generation cardio-kidney-metabolic outcome frameworks, which propose explicit design principles emphasizing integrated endpoints, careful patient selection, and robust trial architectures. When PSA is included as a continuous safety variable rather than a binary screening test, it fits naturally within these multi-domain outcome structures.

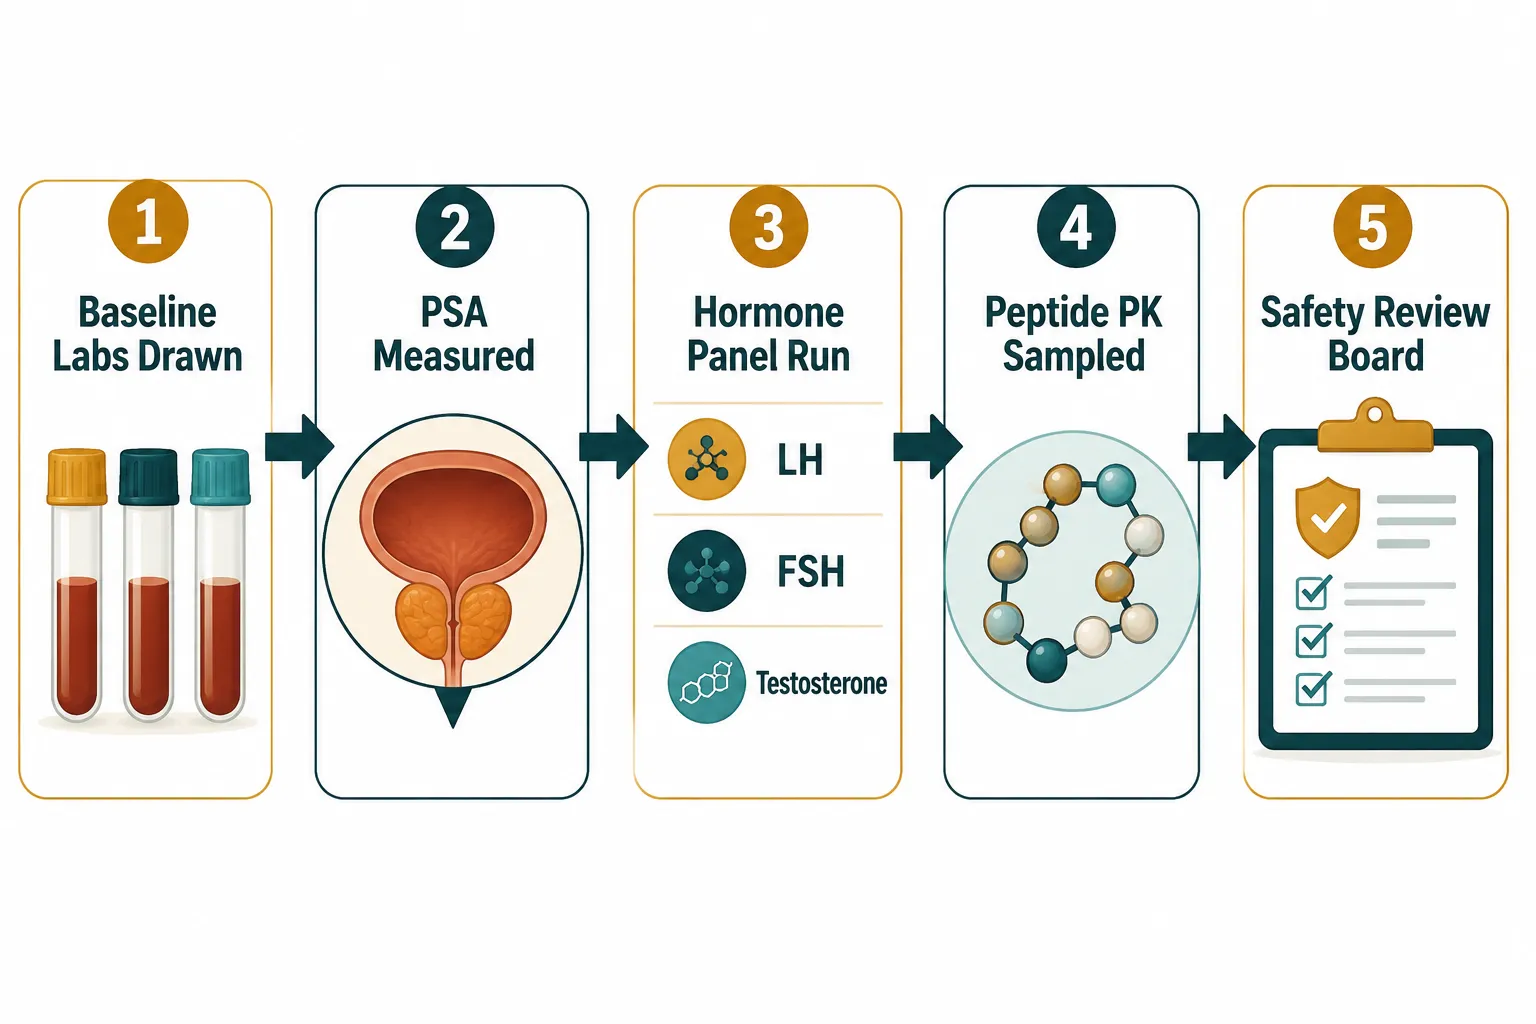
Practical checklist for integrated hormone study design:

  • Define androgen exposure with testosterone, LH, FSH at baseline and each visit
  • Include PSA at minimum at baseline, 3 months, and endpoint
  • Add peptide-specific PK sampling windows aligned with dosing intervals
  • Pre-specify PSA thresholds that trigger dose hold or discontinuation
  • Align FDA engagement strategy (pre-IND, Type C, pre-NDA meetings) with study design milestones

For labs sourcing research-grade compounds, ensuring purity is non-negotiable. Lab tested peptides with verified certificates of analysis are the baseline standard for any protocol that will generate safety data intended for regulatory review.

Conclusion

The intersection of Prostate Specific Antigen, Enclomiphene, and Peptide Hormones in modern hormone study design is not accidental, it reflects the biological reality that androgen modulation, receptor selectivity, and peptide signaling all converge on shared safety endpoints. PSA is not simply a prostate cancer screening tool; it is a dynamic androgenic biomarker that belongs in every male hormone study protocol.

Actionable next steps for researchers and clinicians:

  1. Include PSA as a continuous safety variable in any serm or androgen-modulating protocol, with pre-specified thresholds for dose adjustment.
  2. Apply GLP-1 trial design principles, ascending dose, randomized, double-blind, composite endpoints, to novel peptide programs wherever regulatory precedent is limited.
  3. Use real-world prescribing data and existing pharmacokinetic datasets to power sample sizes and reduce phase II risk.
  4. Engage FDA early through pre-IND meetings when an investigational compound has a structural relationship to an approved drug, as enclomiphene's path illustrates.
  5. Source only verified, lab tested peptides for any study generating data intended for regulatory submission.

Rigorous study design, comprehensive biomarker panels, and early regulatory alignment are the pillars that turn promising hormone research into actionable clinical evidence.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-enclomiphene-and-peptide-hormones-how-labs-design-serm.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-05 13:05:452026-09-05 13:05:45Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies
Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides

Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides

September 1, 2026/0 Comments/in Uncategorized/by

Men with obesity-related secondary hypogonadism can show testosterone levels up to 30% lower than age-matched lean controls, yet the endocrine axis disruption extends far beyond a single hormone. Understanding estrogen receptors, enclomiphene, and peptide hormones: how serms interface with GLP-class and growth hormone peptides is now central to advanced endocrine research protocols that model multiple hormonal axes simultaneously. As GLP-1 receptor agonists and GHRH analogues become fixtures in metabolic and body-composition research, the question of how a selective estrogen receptor modulator like enclomiphene fits into those multi-peptide frameworks has become increasingly important.

Key Takeaways

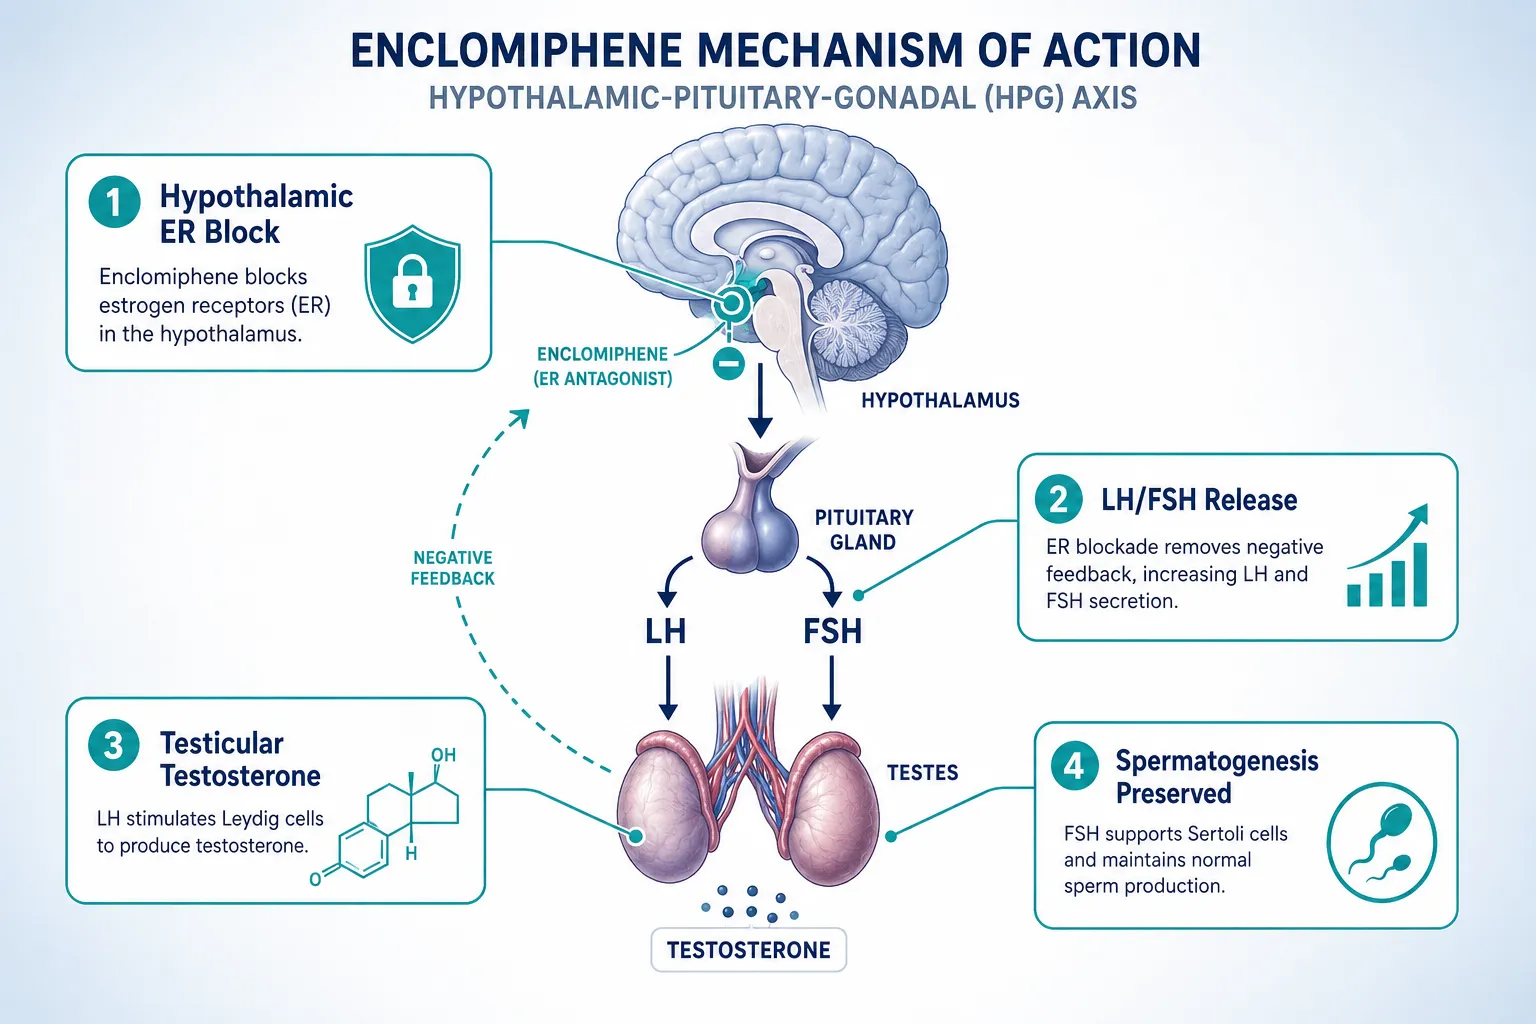
  • Enclomiphene blocks hypothalamic estrogen receptors to raise LH, FSH, and endogenous testosterone without suppressing spermatogenesis.
  • Systematic evidence shows serms can increase total testosterone by a mean of roughly 274 ng/dL versus placebo in functional hypogonadism.
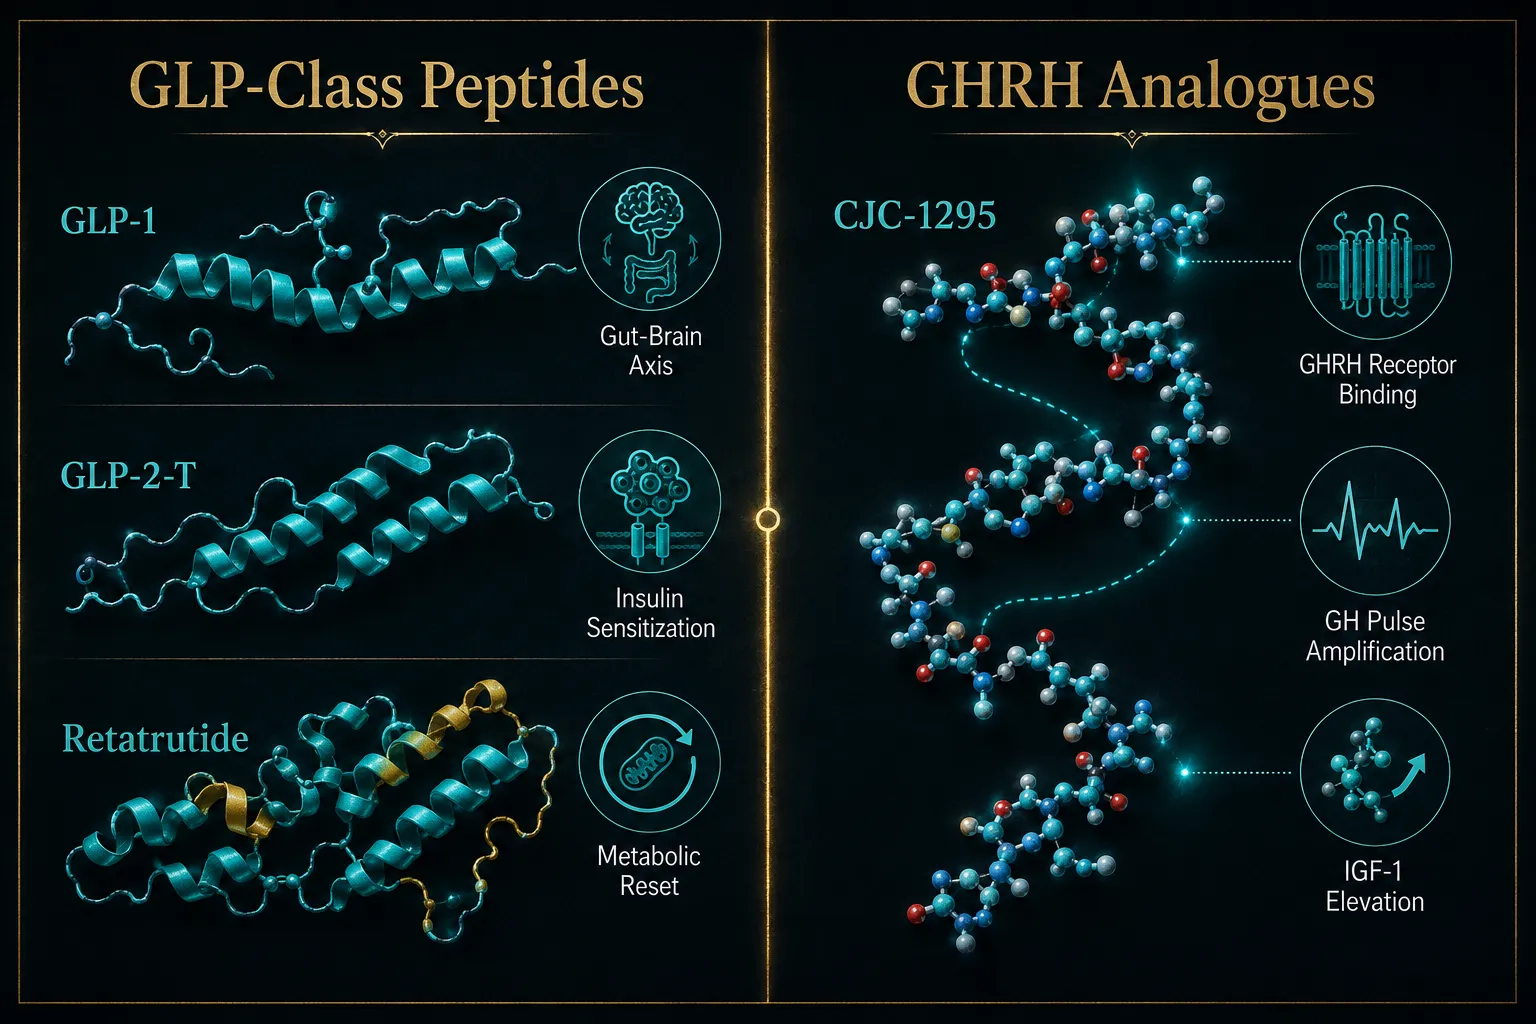
  • GLP-class peptides such as Retatrutide and GLP-2-T act on gut-brain and metabolic axes that indirectly influence sex hormone binding and HPG axis tone.
  • GHRH analogues like CJC-1295 amplify growth hormone pulses and raise IGF-1, creating a separate but intersecting endocrine signal relevant to serm protocols.
  • Formal combination trials of enclomiphene with GLP-class or GHRH peptides remain an open research frontier as of 2026.

How Enclomiphene Modulates Estrogen Receptors in the HPG Axis

Enclomiphene is the trans-isomer of clomiphene. Unlike its cis-isomer zuclomiphene, it acts as a clean antagonist at hypothalamic estrogen receptors, blocking the negative feedback signal that estrogen normally sends to suppress gonadotropin-releasing hormone. The result is a coordinated rise in luteinizing hormone (LH) and follicle-stimulating hormone (FSH), which in turn drives endogenous testicular testosterone production.

How Enclomiphene Modulates Estrogen Receptors in the HPG Axis

This mechanism distinguishes enclomiphene sharply from exogenous testosterone replacement. Testosterone replacement shuts down the HPG axis through negative feedback; enclomiphene does the opposite. A systematic review and meta-analysis of ten randomized controlled trials covering 819 men found that serm therapy, primarily clomiphene and enclomiphene, raised total testosterone by a mean of approximately 274 ng/dL compared with placebo, while sperm parameters remained intact.

A 2026 British Society for Sexual Medicine position statement reinforces this picture. In one referenced RCT of 44 men, daily enclomiphene was non-inferior to transdermal testosterone at both 24 hours and 6 weeks. A retrospective series of 66 men showed a median testosterone increase of 5.76 nmol/L after roughly 9 months of therapy. For researchers exploring serm therapy protocols, these figures establish a meaningful hormonal baseline.

Why metabolic context matters: Men with obesity, type 2 diabetes, or metabolic syndrome often present with reversible hypothalamic-pituitary dysfunction, a profile where enclomiphene's upstream mechanism is particularly well-matched. Elevated aromatase activity in adipose tissue converts more testosterone to estradiol, deepening the hypothalamic feedback suppression that enclomiphene is designed to interrupt.

"Enclomiphene's value lies not just in raising testosterone, but in preserving the entire upstream signaling architecture, a distinction that matters enormously when modeling multi-axis endocrine protocols."

GLP-Class Peptides and Their Indirect Influence on Estrogen Receptor Signaling

The GLP-class of peptides, including GLP-1 receptor agonists, the dual/triple agonist Retatrutide (GLP-1/GIP/glucagon), and GLP-2-T analogues, operate primarily on gut-brain signaling, insulin secretion, and energy homeostasis. Their connection to estrogen receptor biology is indirect but mechanistically significant.

GLP-Class Peptides and Their Indirect Influence on Estrogen Receptor Signaling

GLP-1 receptor agonists reduce adipose mass. Because adipose tissue is the primary peripheral site of aromatase-driven estrogen synthesis in men, a meaningful reduction in fat mass lowers circulating estradiol. Lower estradiol reduces the hypothalamic estrogen receptor load that enclomiphene must overcome. In practical terms, a subject on a GLP-class agent may show a more responsive HPG axis to serm intervention.

Retatrutide, as a triple agonist targeting GLP-1, GIP, and glucagon receptors, produces more pronounced body-composition shifts than single-agonist agents. Research on tirzepatide peptide, a dual GLP-1/GIP agonist with a related mechanism, illustrates how GLP-class compounds can reshape the metabolic environment in which hormonal axes operate.

GLP-2-T analogues primarily target intestinal epithelial GLP-2 receptors, influencing gut integrity and nutrient absorption. Their relevance to estrogen receptor cross-talk is more distal but may include effects on enterohepatic estrogen recirculation, a pathway that modulates systemic estradiol levels and, consequently, hypothalamic feedback tone.

Researchers working with single peptide protocols often note that isolating one axis at a time provides cleaner data before combining agents, a principle that applies directly to serm-plus-GLP-class study design.

GHRH Analogues, Growth Hormone Peptides, and serm Protocol Integration

CJC-1295 is a synthetic GHRH analogue that extends the half-life of endogenous GHRH, amplifying pulsatile growth hormone release from the anterior pituitary and raising downstream IGF-1 levels. This creates a third endocrine axis, the GH/IGF-1 axis, that intersects with both the HPG axis and the metabolic effects of GLP-class peptides.

GHRH Analogues, Growth Hormone Peptides, and serm Protocol Integration

The relevance to estrogen receptor biology is bidirectional. IGF-1 has been shown to modulate estrogen receptor expression in multiple tissue types. Elevated GH and IGF-1 also influence body composition, reducing fat mass and increasing lean tissue, which feeds back into aromatase activity and circulating estradiol, the same variable that enclomiphene targets at the receptor level.

For researchers modeling endocrine axes, the interaction matrix looks like this:

Agent Primary Target Indirect Effect on ER Signaling
Enclomiphene Hypothalamic ER Direct blockade, raises LH/FSH
GLP-1/Retatrutide GLP-1/GIP/Glucagon R Reduces adipose aromatase substrate
CJC-1295 GHRH receptor IGF-1 modulates ER expression; body comp shift
GLP-2-T Intestinal GLP-2 R Enterohepatic estrogen recirculation effects

Researchers exploring serms in combination with growth hormone peptides should account for these intersecting signals when designing outcome measures. Sports peptides research has long recognized that GH-axis and sex-hormone-axis interventions produce non-additive effects, a principle that extends to serm-plus-GHRH analogue modeling.

Enclomiphene's clinical profile also makes it suitable for populations where erythrocytosis risk from testosterone replacement is a concern, a relevant consideration when subjects are simultaneously on GH-stimulating peptides that affect red blood cell precursor signaling.

As of 2026, formal combination trials pairing enclomiphene with GLP-class agents or GHRH analogues have not been published. This represents a significant gap in the literature and a clear frontier for structured research protocols.

Conclusion

The intersection of estrogen receptors, enclomiphene, and peptide hormones, how serms interface with GLP-class and growth hormone peptides, is one of the most mechanistically rich areas in current endocrine research. Enclomiphene provides a targeted, fertility-preserving tool for HPG axis restoration. GLP-class peptides reshape the metabolic environment that determines how much estrogenic feedback the hypothalamus receives. GHRH analogues like CJC-1295 add a third dimension through IGF-1-mediated effects on receptor expression and body composition.

Actionable next steps for researchers and clinicians:

  • Map baseline estradiol, LH, FSH, and testosterone before introducing any multi-agent protocol.
  • Consider GLP-class-driven fat-mass reduction as a preparatory phase that may enhance enclomiphene responsiveness.
  • Use validated assays for both total and free testosterone, IGF-1, and estradiol when modeling combined serm-plus-peptide protocols.
  • Monitor spermatogenesis parameters if fertility preservation is a stated research or clinical objective.
  • Prioritize single-axis baseline data before combining enclomiphene with GHRH analogues to isolate each variable's contribution.

The endocrine axes do not operate in isolation. Research protocols that treat them as interconnected systems, rather than independent targets, will generate the most meaningful data as this field matures.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/estrogen-receptors-enclomiphene-and-peptide-hormones-how-serms-interface-with-gl.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-01 13:05:082026-09-01 13:05:08Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides
Peptides and Polypeptides in Endocrine Pharmacology: How Enclomiphene Interfaces With Estrogen Receptor Biology

Peptides and Polypeptides in Endocrine Pharmacology: How Enclomiphene Interfaces With Estrogen Receptor Biology

August 1, 2026/0 Comments/in Uncategorized/by

Fewer than 10% of clinicians who prescribe selective estrogen receptor modulators can accurately define the structural difference between a peptide hormone and a small-molecule serm, yet that distinction determines how each drug class reshapes the endocrine axis. Peptides and polypeptides in endocrine pharmacology represent one of the most mechanistically rich areas of modern pharmacology, and understanding where non-peptide agents like enclomiphene fit within that landscape is essential for anyone conducting or interpreting research in this field.

Key Takeaways

  • Peptide and polypeptide hormones act on cell-surface receptors through second-messenger cascades, while enclomiphene binds directly inside the nucleus at estrogen receptors.
  • Enclomiphene works as an estrogen receptor antagonist at the hypothalamus, disrupting negative feedback and increasing endogenous LH and FSH secretion.
  • The hypothalamic-pituitary-gonadal (HPG) axis is the shared regulatory highway for both peptide-based and small-molecule endocrine modulators.
  • Purity and characterization of research compounds, whether peptide or small molecule, directly affect the reliability of mechanistic data.
  • Combining knowledge of peptide receptor biology with serm pharmacology produces a more complete picture of hormonal signaling networks.

The Structural Divide: Peptide Hormones Versus Small-Molecule Modulators

To appreciate how enclomiphene interfaces with estrogen receptor biology, it helps to first anchor the broader category of peptides and polypeptides in endocrine pharmacology.

Peptide hormones are chains of amino acids. Short chains of 2-50 residues are typically called peptides; longer chains become polypeptides and, eventually, proteins. Examples include gonadotropin-releasing hormone (GnRH), luteinizing hormone (LH), follicle-stimulating hormone (FSH), and growth hormone-releasing hormone (GHRH). These molecules are too large and too hydrophilic to cross the cell membrane, so they bind to surface receptors and trigger intracellular signaling cascades, most commonly through cyclic AMP or phospholipase C pathways.

Research into peptide modulators spans a wide range of targets. For instance, BPC-157 and TB-500 peptide research explores tissue-signaling mechanisms that share conceptual overlap with endocrine feedback loops. Similarly, GLP-1 peptide sourcing and research illustrates how incretin-class peptides modulate metabolic signaling through surface-receptor mechanisms, a useful structural contrast to nuclear receptor pharmacology.

Small-molecule agents like enclomiphene are chemically synthesized, low-molecular-weight compounds. They are lipophilic enough to diffuse across cell membranes and interact directly with intracellular receptors, in this case, the estrogen receptor (ER), a nuclear receptor superfamily member.

"The key pharmacological divide is not potency, it is receptor location. Peptide hormones knock on the cell's front door; small-molecule serms walk straight into the nucleus."

The Structural Divide: Peptide Hormones Versus Small-Molecule Modulators

How Enclomiphene Interfaces With Estrogen Receptor Biology Within the HPG Axis

The hypothalamic-pituitary-gonadal (HPG) axis is the shared regulatory highway where both peptide hormones and small-molecule modulators exert their effects.

Under normal physiology, circulating estradiol binds to estrogen receptors in hypothalamic neurons and pituitary gonadotrophs. This binding suppresses GnRH pulse frequency and reduces LH and FSH secretion, a classic negative-feedback loop mediated by a steroid hormone acting on nuclear receptors.

Enclomiphene, the trans-isomer of clomiphene citrate, competitively occupies estrogen receptors at these same hypothalamic and pituitary sites. Because it acts as a selective estrogen receptor antagonist in these tissues, it blocks estradiol's inhibitory signal. The hypothalamus interprets this blockade as low circulating estrogen, responds by increasing GnRH pulse amplitude, and the pituitary responds with elevated LH and FSH output.

The downstream result is stimulation of endogenous gonadal steroidogenesis, a fundamentally different mechanism from direct peptide hormone replacement. Compare this to tesa, a synthetic GHRH analog that binds surface receptors on pituitary somatotrophs to stimulate growth hormone release. Both agents ultimately raise a downstream hormone, but through entirely different receptor classes and cellular compartments.

Tissue-Selective Receptor Modulation

Enclomiphene's selectivity is tissue-dependent. In the hypothalamus and pituitary, it behaves as an antagonist. In other tissues, such as bone, estrogenic agonist activity may be partially preserved. This tissue selectivity is what defines the broader serm class and distinguishes these agents from pure estrogen blockers.

Feature Peptide Hormones Enclomiphene (serm)
Receptor location Cell surface Nuclear (intracellular)
Mechanism Second-messenger cascade Direct DNA transcription modulation
Tissue selectivity Determined by receptor subtype Determined by co-activator expression
Route of action Extracellular binding Intracellular ligand-binding domain

Peptides and Polypeptides in Endocrine Pharmacology: Research Sourcing and Compound Integrity

Peptides and Polypeptides in Endocrine Pharmacology: Research Sourcing and Compound Integrity

Peptides and Polypeptides in Endocrine Pharmacology: Research Sourcing and Compound Integrity

For researchers working across both peptide and small-molecule endocrine pharmacology, compound purity is a non-negotiable variable. Mechanistic studies that use impure or mischaracterized compounds produce data that cannot be replicated or translated.

This principle applies equally to peptide-based endocrine research tools. The GHK-Cu copper peptide research and sourcing guide addresses quality benchmarks relevant to any peptide used in signaling research. Likewise, the BPC-157 core documentation and first research guide outlines documentation standards that set a useful precedent for characterizing any endocrine research compound.

When sourcing peptides for studies that sit adjacent to serm pharmacology research, for example, examining GnRH analog interactions or LH pulse dynamics, researchers benefit from working with lab-tested peptides that carry third-party certificates of analysis. The same rigor should be applied to any small-molecule comparator used in parallel assays.

Three sourcing standards that apply across compound classes:

  1. Certificate of Analysis (CoA), confirms identity and purity by HPLC and mass spectrometry
  2. Sterility testing, essential for any in vivo research application
  3. Stability data, particularly relevant for peptides, which degrade faster than most small molecules under improper storage conditions

For researchers exploring the growth hormone-releasing axis alongside HPG axis modulators, resources on GHRP-2 versus sermorelin provide useful mechanistic context on how peptide secretagogues differ from receptor-level modulators like enclomiphene.

Conclusion

Peptides and polypeptides in endocrine pharmacology and small-molecule agents like enclomiphene occupy different receptor compartments, but they converge on the same hormonal axes. Enclomiphene's antagonism at hypothalamic and pituitary estrogen receptors reshapes the HPG axis through nuclear receptor biology, a mechanism that is structurally and functionally distinct from the surface-receptor signaling used by GnRH, LH, FSH, and synthetic peptide analogs.

Actionable next steps for researchers:

  • Map the receptor class (surface vs. nuclear) of every agent used in an endocrine study before designing assays.
  • Source all peptide and small-molecule research compounds with documented CoA, sterility, and stability data.
  • When studying HPG axis dynamics, consider how serm-mediated changes in gonadotropin output interact with any co-administered peptide modulators.
  • Review mechanistic literature on tissue-selective ER modulation to contextualize enclomiphene's differential effects across target tissues.

Understanding the structural and mechanistic divide between peptide hormones and nuclear receptor modulators is not academic trivia, it is the foundation of reproducible, translatable endocrine pharmacology research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/peptides-and-polypeptides-in-endocrine-pharmacology-how-enclomiphene-interfaces.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-01 13:04:512026-08-01 13:04:51Peptides and Polypeptides in Endocrine Pharmacology: How Enclomiphene Interfaces With Estrogen Receptor Biology
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top