

Peptide Research Safety Monitoring: Hemoglobin, Hematocrit, Liver Enzymes, Glucose, and Blood-Pressure Readouts
{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Peptide Research Safety Monitoring' in crisp white sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge. Background: editorial close-up of a clinical laboratory setting showing glass vials of clear peptide solution, a digital blood pressure monitor, and printed lab reports with highlighted values for hemoglobin, liver enzymes, and glucose, clean, bright studio lighting with cool teal and navy color palette, magazine-cover polish, high contrast, no dark moody tones.","content":["Four-panel labelled infographic diagram (1536×1024) titled 'Core Safety Markers in Peptide Research' on a clean white background with teal-and-navy palette. Panel 1: illustrated red blood cell cluster labeled 'Hemoglobin g/dL' with callout 'Normal: 12-17 g/dL'. Panel 2: hematocrit percentage bar chart labeled 'Hematocrit %' with callout 'Watch >52% threshold'. Panel 3: liver enzyme vial labeled 'ALT / AST Units/L' with callout 'Stop rule: 3x ULN'. Panel 4: glucose meter labeled 'Fasting Glucose mg/dL' with callout 'HbA1c baseline flag'. Thin callout lines, short bullet labels 1-5 words each, editorial medical-guide style, bright studio lighting.","Annotated step-by-step numbered flow diagram (1536×1024) showing peptide research monitoring timeline on a pale blue background with charcoal typography. Step 1 card: 'Baseline Labs, Week 0' with icons for CBC and CMP. Step 2 card: 'Mid-Protocol Check, Week 4' with blood pressure cuff icon. Step 3 card: 'Post-Cycle Panel, Week 8' with liver enzyme flask icon. Step 4 card: 'Quarterly Follow-Up' with glucose meter icon. Each step connected by a bold arrow, short 2-5 word labels per card, callout lines pointing to specific marker names, clean infographic style, teal accent color, high editorial clarity.","Split-screen editorial comparison image (1536×1024): left half shows a warm-lit researcher's desk with a printed CBC report highlighting hemoglobin and hematocrit rows, a stethoscope, and handwritten stop-rule notes; right half shows a digital dashboard mockup displaying liver enzyme trend lines (ALT/AST), a fasting glucose graph, and a blood pressure reading widget in a modern dark-mode interface. Sharp dividing line down the center, short labels 'Wet Lab Markers' on left and 'Digital Monitoring Dashboard' on right, high-contrast magazine composition, cool blue and warm amber palette contrast, editorial quality."]

Fewer than 40% of researchers who work with bioactive peptides establish a formal lab-monitoring schedule before beginning a protocol, a gap that can turn subtle physiological shifts into serious, undetected problems. Rigorous peptide research safety monitoring: hemoglobin, hematocrit, liver enzymes, glucose, and blood-pressure readouts is not optional bookkeeping; it is the scientific backbone that separates responsible inquiry from guesswork. Whether the focus is tissue-repair peptides, growth-hormone secretagogues, or metabolic analogues, each compound class stresses different organ systems in different ways, and the lab panel must reflect that specificity.
Key Takeaways
- A baseline complete blood count (CBC) and comprehensive metabolic panel (CMP) should be established before any peptide protocol begins.
- Hemoglobin and hematocrit are the primary red-flag markers for erythropoietic peptides and GH secretagogues; a hematocrit above 52% is a widely recognized pause threshold.
- ALT and AST elevations above three times the upper limit of normal (3x ULN) represent a standard clinical stop rule for hepatotoxicity.
- Fasting glucose and HbA1c are essential for GLP-1-class and metabolic peptides because baseline insulin resistance can confound interpretation.
- Blood pressure must be tracked alongside hematocrit because rising red-cell mass directly increases cardiovascular load.
Understanding the Core Lab Panel for Peptide Safety Monitoring

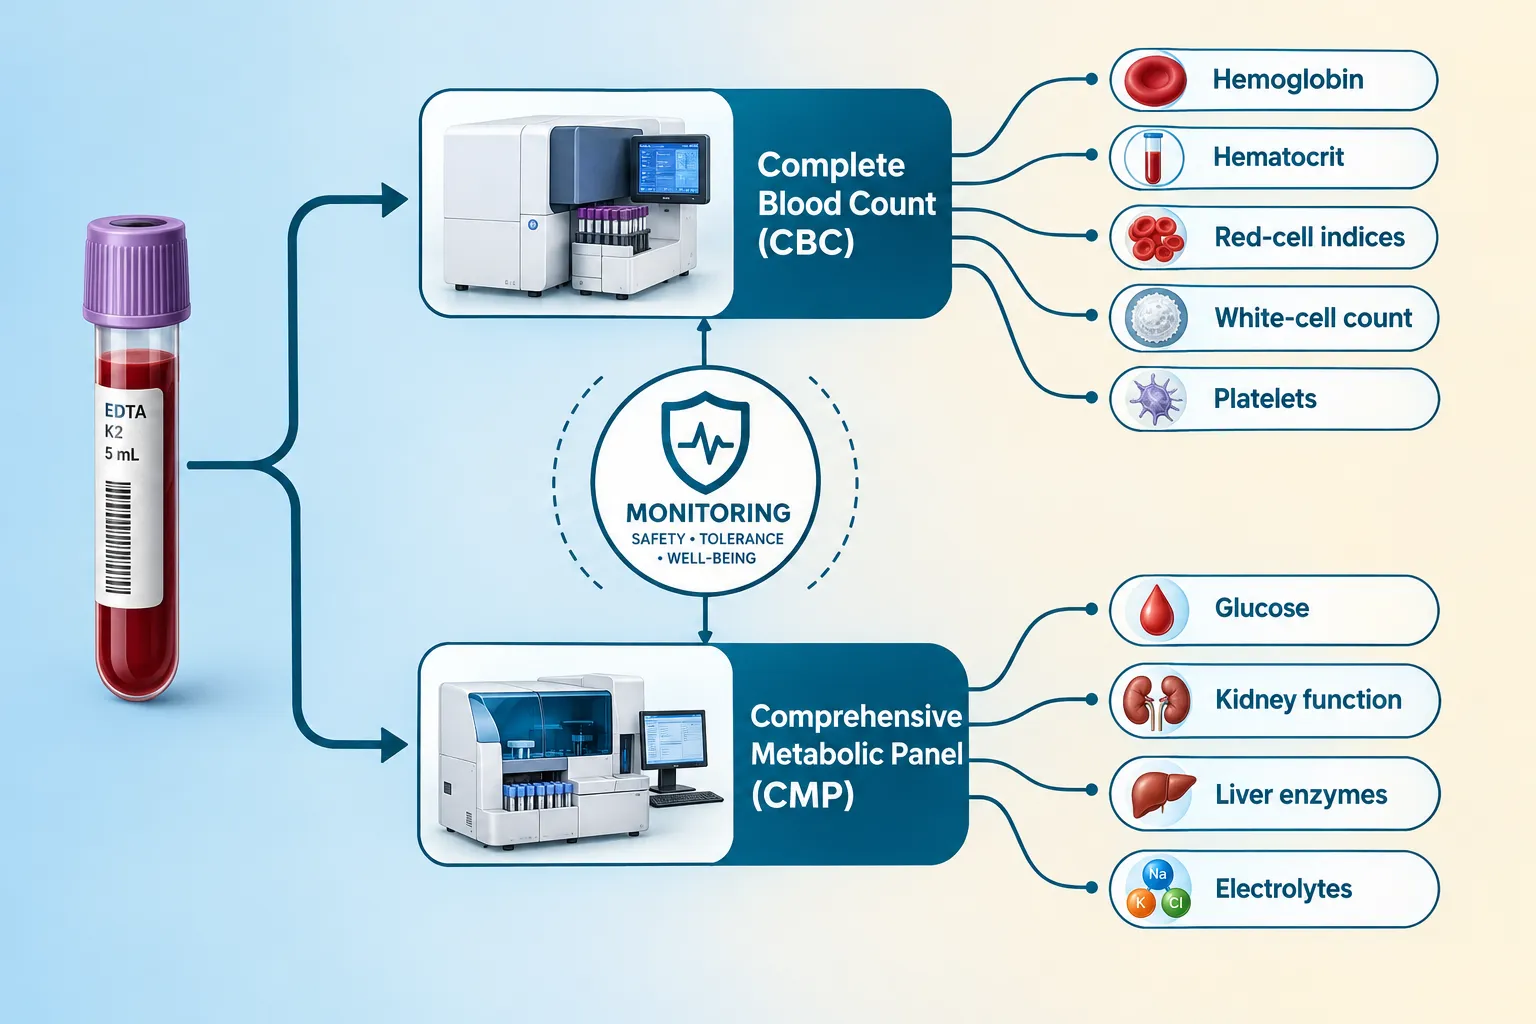
Every responsible monitoring program starts with two foundational tests: a complete blood count (CBC) and a comprehensive metabolic panel (CMP). The CBC captures hemoglobin, hematocrit, red-cell indices, white-cell count, and platelets. The CMP adds glucose, kidney function markers, and the liver enzymes ALT, AST, alkaline phosphatase, and bilirubin. Together, these two panels cover the most common adverse-effect pathways seen across peptide classes.
Hemoglobin measures the oxygen-carrying protein inside red blood cells, expressed in grams per deciliter (g/dL). Normal ranges sit roughly between 12 and 17 g/dL depending on biological sex. Hematocrit is the percentage of blood volume occupied by red cells, with a general healthy range of 36-50%. Growth-hormone secretagogues such as tesa and ipamorelin can stimulate IGF-1 production, which in turn promotes erythropoiesis. Elevated hematocrit thickens blood viscosity and raises clotting risk, which is why most clinicians treating research subjects apply a pause-and-reassess rule when hematocrit exceeds 52%.
Confounding factors matter here. Dehydration artificially inflates hematocrit. Chronic iron deficiency suppresses hemoglobin even when a peptide is actively stimulating red-cell production. Documenting hydration status and iron stores at baseline prevents misreading the data mid-protocol.
"A single out-of-range lab value means little without a baseline. Context is everything in peptide research safety monitoring."
For researchers comparing compounds, resources like the LL-37 versus SS-31 benefits of each peptide overview illustrate how two peptides in the same general category can have very different physiological footprints, reinforcing why class-specific monitoring matters.
Liver Enzymes and Glucose: Action Thresholds in Peptide Research Safety Monitoring
Liver Enzyme Thresholds
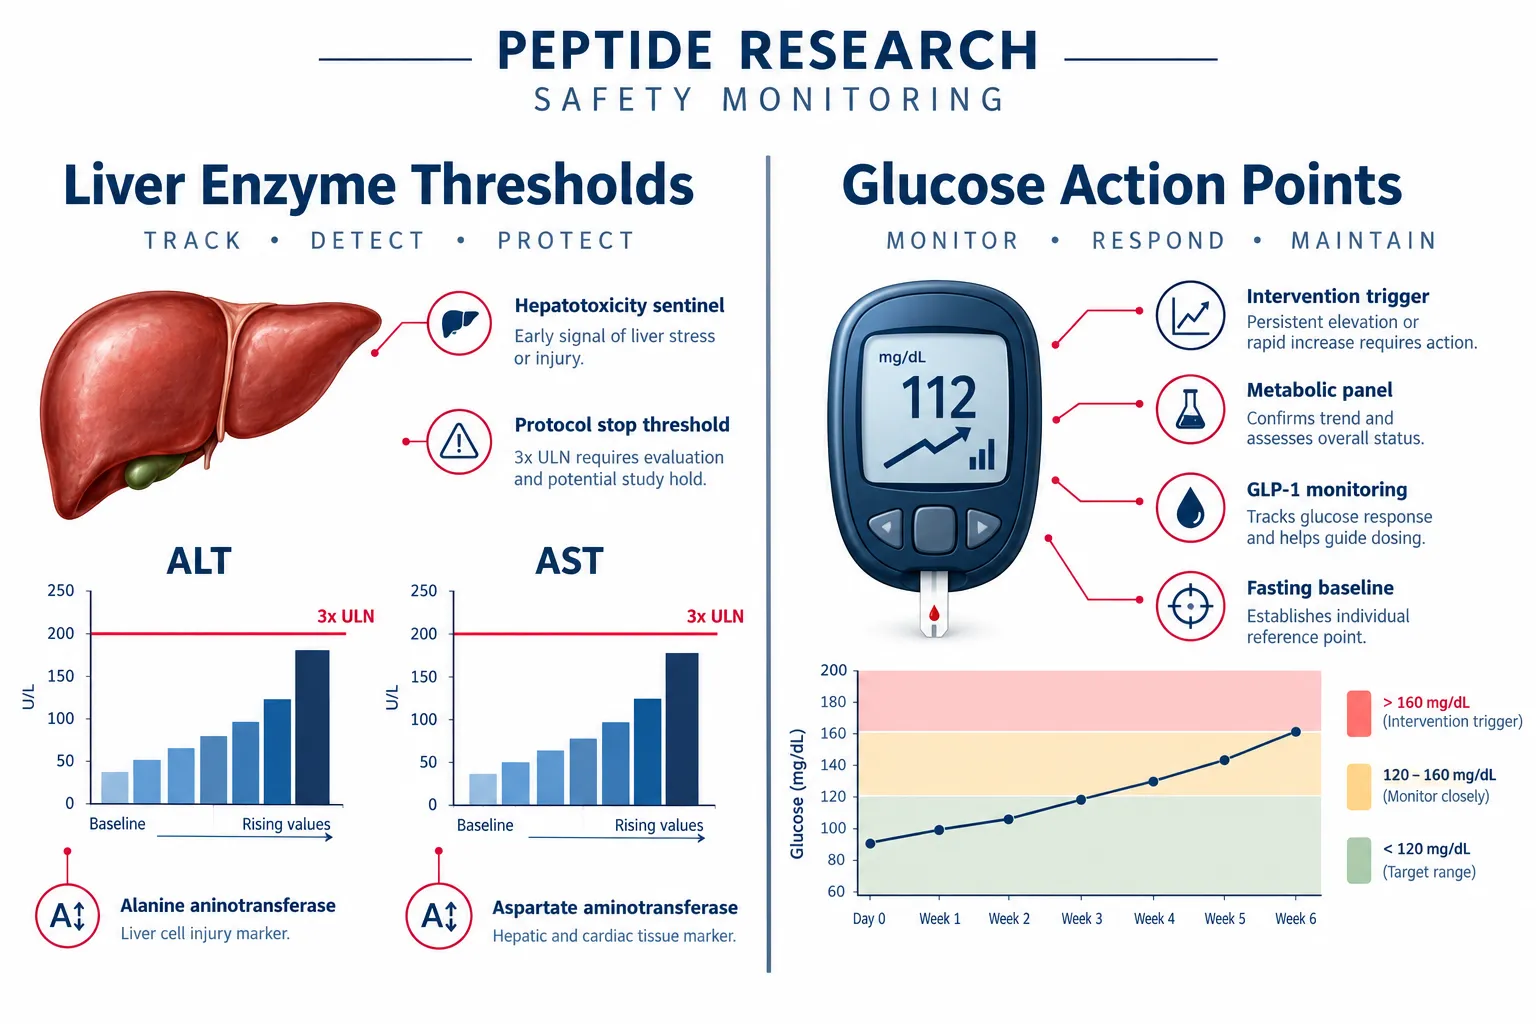
ALT (alanine aminotransferase) and AST (aspartate aminotransferase) are the primary hepatotoxicity sentinels. The 3x ULN rule is the most widely applied stop threshold: if either enzyme rises above three times the laboratory's upper limit of normal, the protocol should pause and the subject should be reassessed. At 5x ULN, most clinical frameworks call for immediate discontinuation.
Several factors can inflate baseline liver enzymes independent of any peptide:
| Confounding Factor | Effect on ALT/AST |
|---|---|
| Non-alcoholic fatty liver disease | Chronically elevated baseline |
| Intense resistance training | Transient AST elevation (muscle origin) |
| Alcohol consumption | Raises both ALT and AST |
| Statin medications | Can elevate transaminases |
| Thyroid dysfunction | Alters enzyme clearance rates |
Because intense exercise raises AST from skeletal muscle, not the liver, researchers should note training intensity in the protocol log. If AST is elevated but ALT is normal and the AST/ALT ratio is above 2:1, muscle origin is the more likely explanation.
Tissue-repair peptides such as GHK-Cu and BPC-157 have limited formal hepatotoxicity data. Researchers sourcing these compounds should prioritize verified purity, as contaminants in poorly manufactured peptides are a more common cause of enzyme elevation than the peptide itself. Evaluating purity standards, as discussed in the where to buy research-grade Glow Blend peptide: evaluating purity resource, is a direct risk-reduction step.
Glucose and HbA1c Monitoring
Fasting glucose and glycated hemoglobin (HbA1c) are non-negotiable markers for any protocol involving metabolic peptides. GLP-1 receptor agonist analogues, including newer research compounds like those in the GLP-3 R peptide GA3 category, act on insulin secretion pathways. A subject with undiagnosed pre-diabetes will respond very differently than a metabolically healthy subject, making baseline HbA1c essential for accurate interpretation.
The practical monitoring cadence for glucose markers:
- Baseline, fasting glucose and HbA1c before protocol initiation
- Week 4, fasting glucose repeat, especially for GLP-1 or GH secretagogue protocols
- Week 8 or end of protocol, full CMP including glucose
- Quarterly, HbA1c if the protocol extends beyond 12 weeks
GH-stimulating peptides can cause transient insulin resistance by elevating free fatty acids. This effect is dose-dependent and typically resolves between doses, but it can push a borderline-glucose subject into a clinically significant range without obvious symptoms.
Blood Pressure, Cardiovascular Risk, and Differentiated Monitoring by Peptide Class
Blood pressure is the cardiovascular bridge between hematocrit and metabolic status. Elevated hematocrit increases blood viscosity, which raises peripheral vascular resistance and systolic pressure. Simultaneously, GLP-1-class peptides can modestly reduce blood pressure through natriuretic and vasodilatory mechanisms, a benefit that can become a risk if a subject is already on antihypertensive medication.
Recommended blood pressure monitoring schedule:
- Baseline reading (seated, after 5 minutes of rest, both arms)
- Every 2-4 weeks during active protocol
- At each lab draw visit
A systolic reading consistently above 140 mmHg or a diastolic above 90 mmHg warrants protocol review, particularly when hematocrit is simultaneously trending upward. The two markers together create a compounding cardiovascular risk that neither alone fully captures.
Monitoring by Peptide Class
Different peptide classes stress different systems. The table below summarizes priority markers:
| Peptide Class | Priority Markers | Monitoring Frequency |
|---|---|---|
| GH secretagogues (tesa, ipamorelin) | Hematocrit, fasting glucose, IGF-1 | Every 4-6 weeks |
| GLP-1 analogues | Fasting glucose, HbA1c, blood pressure | Every 4 weeks |
| Tissue-repair peptides (BPC-157, TB-500) | ALT/AST, CBC | Baseline and 8-week |
| Mitochondrial peptides (SS-31) | CBC, CMP, blood pressure | Baseline and 8-week |
For researchers working with mitochondrial-targeted compounds, the SS-31 mechanism and research overview provides useful context on the physiological pathways that monitoring should address. Similarly, understanding the safety profile of combined protocols, such as reviewed in is it safe to combine tesa with CJC ipamorelin, directly informs which additional markers to add when stacking compounds.
Evidence gaps remain significant. BPC-157, TB-500, and GHK-Cu lack large randomized controlled trials in humans. Regulatory status for these compounds as research chemicals means that monitoring frameworks are built from preclinical data, case series, and emerging clinical consensus rather than approved prescribing guidelines. This makes diligent lab tracking more important, not less.
Conclusion
Effective peptide research safety monitoring: hemoglobin, hematocrit, liver enzymes, glucose, and blood-pressure readouts requires a structured, class-specific approach rather than a one-size-fits-all panel. The actionable next steps are clear:
- Establish a full baseline, CBC, CMP, fasting glucose, HbA1c, and a resting blood pressure reading, before any protocol begins.
- Apply recognized stop rules, hematocrit above 52%, liver enzymes above 3x ULN, or sustained blood pressure above 140/90 mmHg each warrant immediate protocol pause.
- Account for confounders, document training intensity, hydration, concurrent medications, and baseline metabolic health to avoid misreading data.
- Match monitoring frequency to compound class, GH secretagogues and GLP-1 analogues require more frequent glucose and cardiovascular checks than tissue-repair peptides.
- Source verified compounds, contaminant-driven enzyme elevations are preventable; working with suppliers who provide third-party purity testing is a direct safety measure.
As the research landscape in 2026 continues to evolve, risk-stratified monitoring protocols are becoming the emerging standard. Researchers who build these habits early will generate cleaner data, protect subject welfare, and contribute more credibly to the growing body of peptide science.


Leave a Reply
Want to join the discussion?Feel free to contribute!