

Metoprolol in Incretin and Growth-Hormone Studies: Separating Heart-Rate Effects From Peptide Responses
Beta-blockers have long been used as tools to control cardiovascular variables in research, but their role in isolating peptide-specific signals is underappreciated. When GLP-1 receptor agonists can raise resting heart rate by as much as 10 beats per minute in some patients, and when growth-hormone release is modulated by adrenergic tone, the question of how to cleanly attribute any observed response to the peptide itself becomes urgent. This is exactly where metoprolol in incretin and growth-hormone studies: separating heart-rate effects from peptide responses becomes a precise and practical strategy.
Key Takeaways
- Metoprolol lowers resting heart rate by approximately 5-7 bpm on average, making it a reliable pharmacological tool to "clamp" heart rate in mechanistic studies.
- GLP-1 receptor agonists raise heart rate by 2-10 bpm depending on the agent, creating a confounding variable that beta-blockade can suppress.
- Beta-adrenergic tone exerts a tonic inhibitory effect on growth-hormone release, meaning metoprolol itself can unmask GH responses.
- Careful baseline and repeated-measure design is essential when using metoprolol as an experimental variable.
- Co-administration of metoprolol with incretin or GH-related peptides is clinically feasible with appropriate monitoring.
Why Beta-Blockade Matters as an Experimental Variable
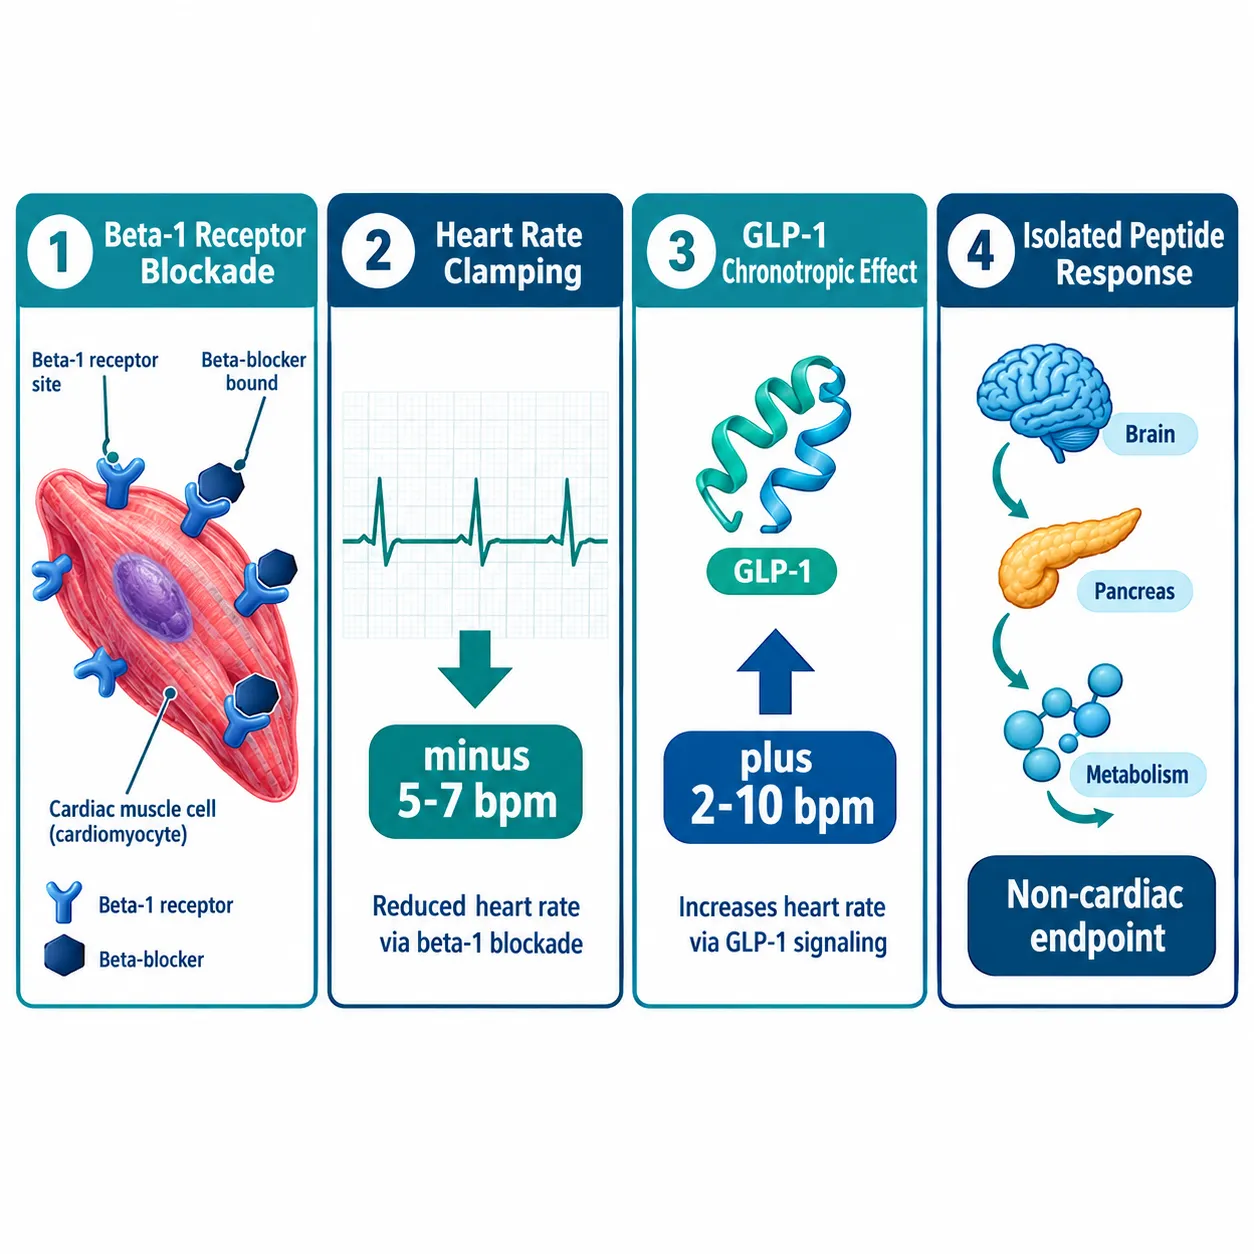
Metoprolol is a beta-1 selective adrenergic blocker. At standard doses, it reduces heart rate, myocardial contractility, and cardiac output both at rest and during exercise. Extended-release metoprolol succinate produces mean resting heart-rate reductions of roughly 5-7 bpm, with some individuals showing larger drops. This predictable, dose-dependent, and reversible effect is exactly what researchers need when designing studies where heart rate must be held steady.
The problem in peptide research is that many bioactive compounds have direct or indirect chronotropic effects. If a study measures glucose metabolism, vascular tone, or endocrine secretion after administering an incretin peptide, an uncontrolled rise in heart rate will alter blood pressure, cardiac output, and tissue perfusion simultaneously. Those changes then confound the metabolic or hormonal readout.
By using metoprolol to suppress the chronotropic component, investigators can attribute downstream effects more confidently to the peptide's direct receptor-mediated actions.
This is not a theoretical exercise. Animal studies have used combined beta-blockade and muscarinic blockade to establish intrinsic heart rate, then shown that peptides like oxyntomodulin can still raise intrinsic heart rate through pathways independent of GLP-1 receptors. That finding only became visible because beta-adrenergic confounding was removed first.
For researchers exploring GH analogue peptides or incretin-based compounds, understanding this pharmacological separation is foundational.
Incretin Peptides and the Chronotropic Problem
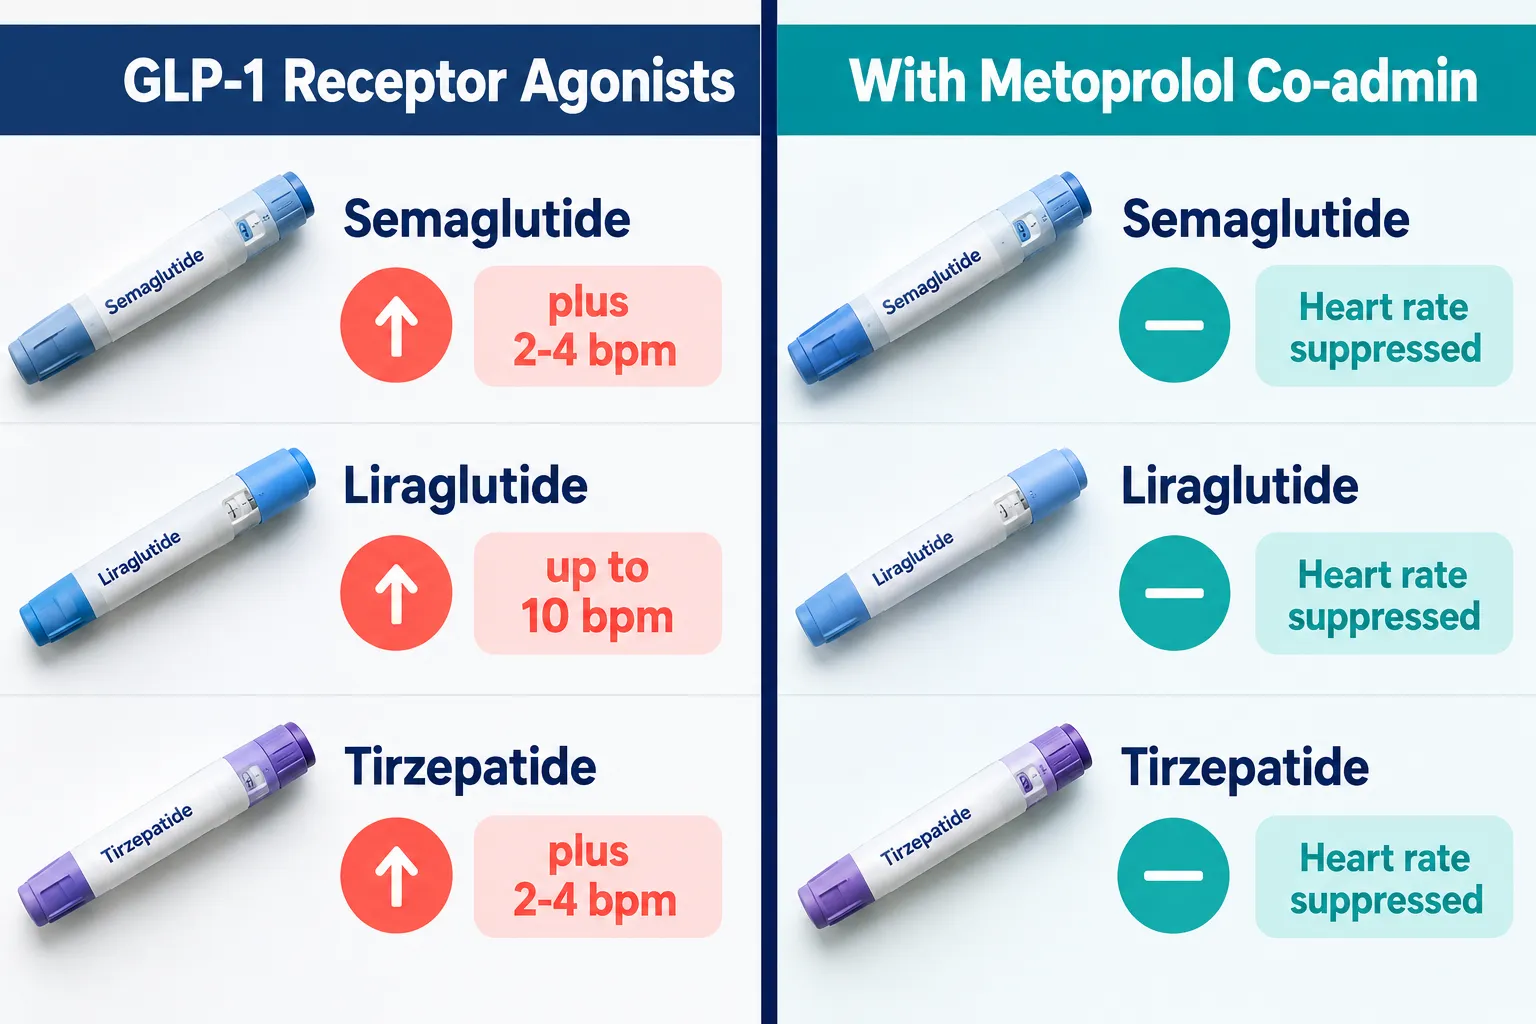
GLP-1 receptor agonists are now central to obesity and diabetes care. Their cardiovascular effects are well documented, but the magnitude of heart-rate elevation varies considerably by agent.
| Agent | Approximate HR Increase |
|---|---|
| Liraglutide | Up to ~10 bpm |
| Semaglutide | ~2-4 bpm |
| Dulaglutide | ~2-4 bpm |
| Tirzepatide | ~2-4 bpm |
| 24-hour average (class) | ~7 bpm |
Real-world data from patients with implantable cardioverter-defibrillators show that starting a GLP-1 receptor agonist raises daily heart rate by a median 1.5 bpm and nighttime heart rate by about 2.0 bpm, with roughly 2.5 bpm additional nighttime increases per dose uptitration. These are small numbers in clinical practice, but in a mechanistic study designed to detect a 3-4 bpm signal, they represent meaningful noise.
"When the peptide-induced heart-rate change is the same order of magnitude as the outcome you are trying to measure, you cannot separate signal from confound without pharmacological control."
This is the core argument for metoprolol in incretin and growth-hormone studies: separating heart-rate effects from peptide responses. Beta-blockade suppresses the chronotropic signal, allowing the researcher to focus on non-cardiac endpoints such as insulin secretion, glucose disposal, or endocrine axis activity.
Researchers interested in weight-loss peptide mechanisms should also review what is the strongest peptide for weight loss for context on how incretin-class compounds compare on metabolic endpoints.
For those studying tesa peptide benefits, the same principle applies: any growth-hormone-releasing peptide that alters autonomic tone will require heart-rate control to isolate the GH-specific signal.
Growth Hormone, Adrenergic Tone, and Metoprolol's Dual Role
Historical endocrine research in animal models demonstrated that central administration of beta-adrenergic antagonists, including metoprolol, produced a gradual elevation in plasma growth hormone, while beta-agonists reduced GH. The conclusion was that beta-adrenergic tone exerts a tonic inhibitory effect on GH release.
This creates a dual consideration for study design:
- Metoprolol suppresses heart rate (the desired confound-control effect).
- Metoprolol may itself unmask or amplify GH responses by removing inhibitory adrenergic input.
Both effects must be accounted for. If a study uses metoprolol to control heart rate during a GH-releasing peptide protocol, the observed GH elevation may reflect both the peptide's action and the removal of adrenergic inhibition. Crossover designs with placebo beta-blockade arms are therefore essential.
For background on how peptides interact with endocrine pharmacology more broadly, the article on peptides and polypeptides in endocrine pharmacology provides useful mechanistic context.
Practical Study Design: Baseline and Repeated-Measure Recommendations
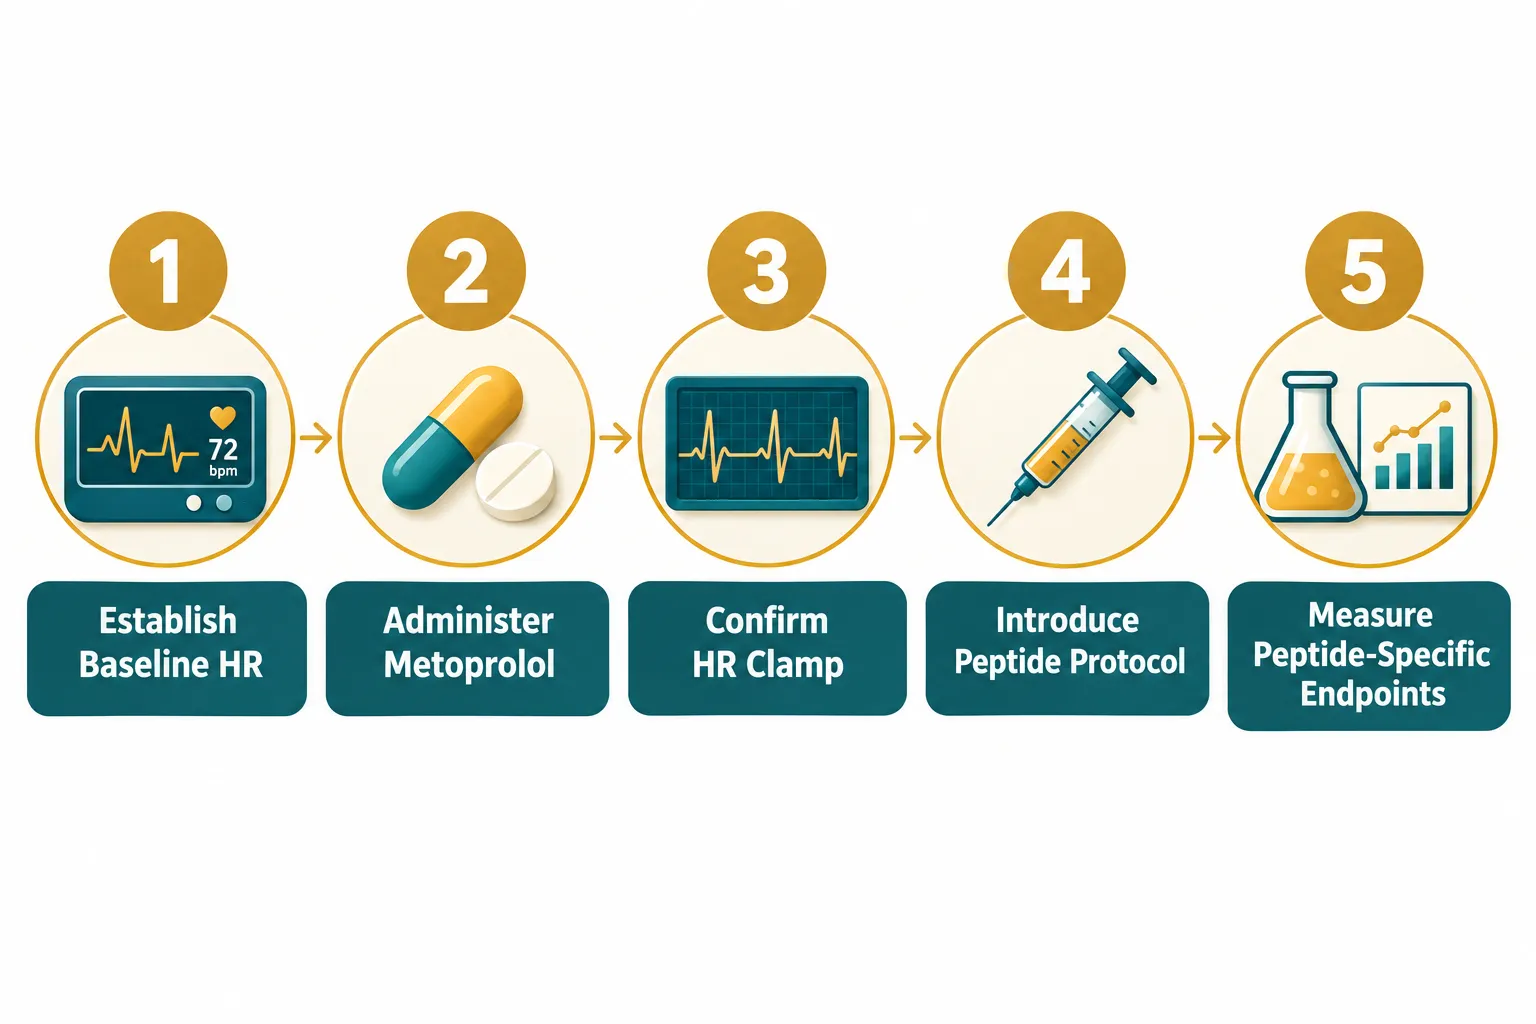
Applying metoprolol in incretin and growth-hormone studies: separating heart-rate effects from peptide responses effectively requires structured protocols. The following recommendations reflect current best practice for mechanistic research designs.
Before starting any intervention:
- Record resting heart rate on at least three separate days to establish a stable baseline.
- Document blood pressure, fasting glucose, and fasting insulin at each baseline visit.
- Confirm that metoprolol has reached steady-state plasma levels (typically 4-5 half-lives after initiation or dose change) before introducing the peptide protocol.
During the study:
- Use continuous or frequent intermittent heart-rate monitoring to confirm the "clamp" is maintained.
- Measure peptide-specific endpoints (e.g., GLP-1 levels, GH pulse amplitude, insulin secretion) at standardized time points relative to peptide administration, not relative to drug administration.
- In crossover designs, allow sufficient washout time for metoprolol; withdrawal data confirm that heart rate normalizes to the mid-60s bpm range after discontinuation, but full washout should be confirmed by repeated measurement rather than assumed from timing alone.
Repeated-measure considerations:
- Collect hormone and metabolic samples at the same time of day across all study arms to control for circadian variation in GH pulsatility and insulin sensitivity.
- Account for exercise tolerance changes: metoprolol blunts exercise-induced tachycardia, so any exercise challenge used to stimulate GH must be standardized by workload output, not by target heart rate.
Understanding peptide dosing protocols is equally important when designing repeated-measure studies, as dose timing relative to beta-blockade will affect the observed peptide response window.
For studies involving mitochondrial or cytoprotective peptides alongside cardiovascular variables, the SS-31 10mg research peptide considerations resource offers relevant parallel design guidance.
Conclusion
The value of metoprolol in incretin and growth-hormone studies lies in its predictability. A 5-7 bpm heart-rate reduction, reliably achieved and reversible, gives researchers a clean pharmacological lever to isolate peptide-specific effects from autonomic noise. The key practical steps are straightforward: establish a stable heart-rate baseline before intervention, confirm steady-state beta-blockade before introducing the peptide, use continuous monitoring to verify the clamp throughout the protocol, and build crossover or placebo-controlled arms to separate metoprolol's own endocrine effects from those of the peptide under study.
As incretin therapies expand in obesity and cardiometabolic medicine, mechanistic trials will increasingly need this kind of pharmacological scaffolding. Researchers and clinicians designing such studies should treat beta-blockade not as a background medication but as an active experimental variable that requires the same rigorous characterization as the peptide itself. Reviewing the broader landscape of peptides 101 for research-use only buyers is a practical next step for anyone building a comprehensive mechanistic protocol.