Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: cardiovascular disease research

Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C

Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C

October 3, 2026/0 Comments/in Uncategorized/by

"

Professional () hero image with 'Retatrutide and Cardiovascular Disease' in crisp white on a deep navy semi-transparent

Cardiovascular disease kills more people with obesity and type 2 diabetes than any other complication, yet most obesity drug trials still define success almost entirely by the number on a scale or a single blood sugar marker. Retatrutide and cardiovascular disease research is now forcing a rethink of that narrow framework, pushing investigators to design endpoints that capture blood pressure, lipid profiles, inflammatory biomarkers, and hard cardiovascular events alongside weight and A1C.

Key Takeaways

  • Retatrutide, a GLP-1/GIP/glucagon triple agonist, produces striking reductions in blood pressure, triglycerides, waist circumference, and high-sensitivity C-reactive protein (hsCRP), signals that go well beyond weight loss and glycemic control.
  • Phase 3 TRIUMPH-3 data showed roughly 22-25% weight reduction at 12 mg, with systolic blood pressure falling up to 10.8 mmHg and hsCRP dropping up to 58%, but cardiovascular event rates did not reach statistical significance.
  • A dedicated cardiovascular outcomes trial (CVOT) is underway, designed specifically to evaluate major adverse cardiovascular events (MACE) in high-risk populations.
  • Distinguishing exploratory cardiometabolic signals from validated cardiovascular-outcome evidence is essential for sound protocol planning and regulatory strategy.
  • Future endpoint frameworks will likely use integrated cardiometabolic composites, covering lipids, inflammation, central adiposity, and organ-specific outcomes, rather than relying on weight and A1C alone.

Why Triple-Agonist Biology Demands Broader Endpoint Thinking
Why Triple-Agonist Biology Demands Broader Endpoint Thinking

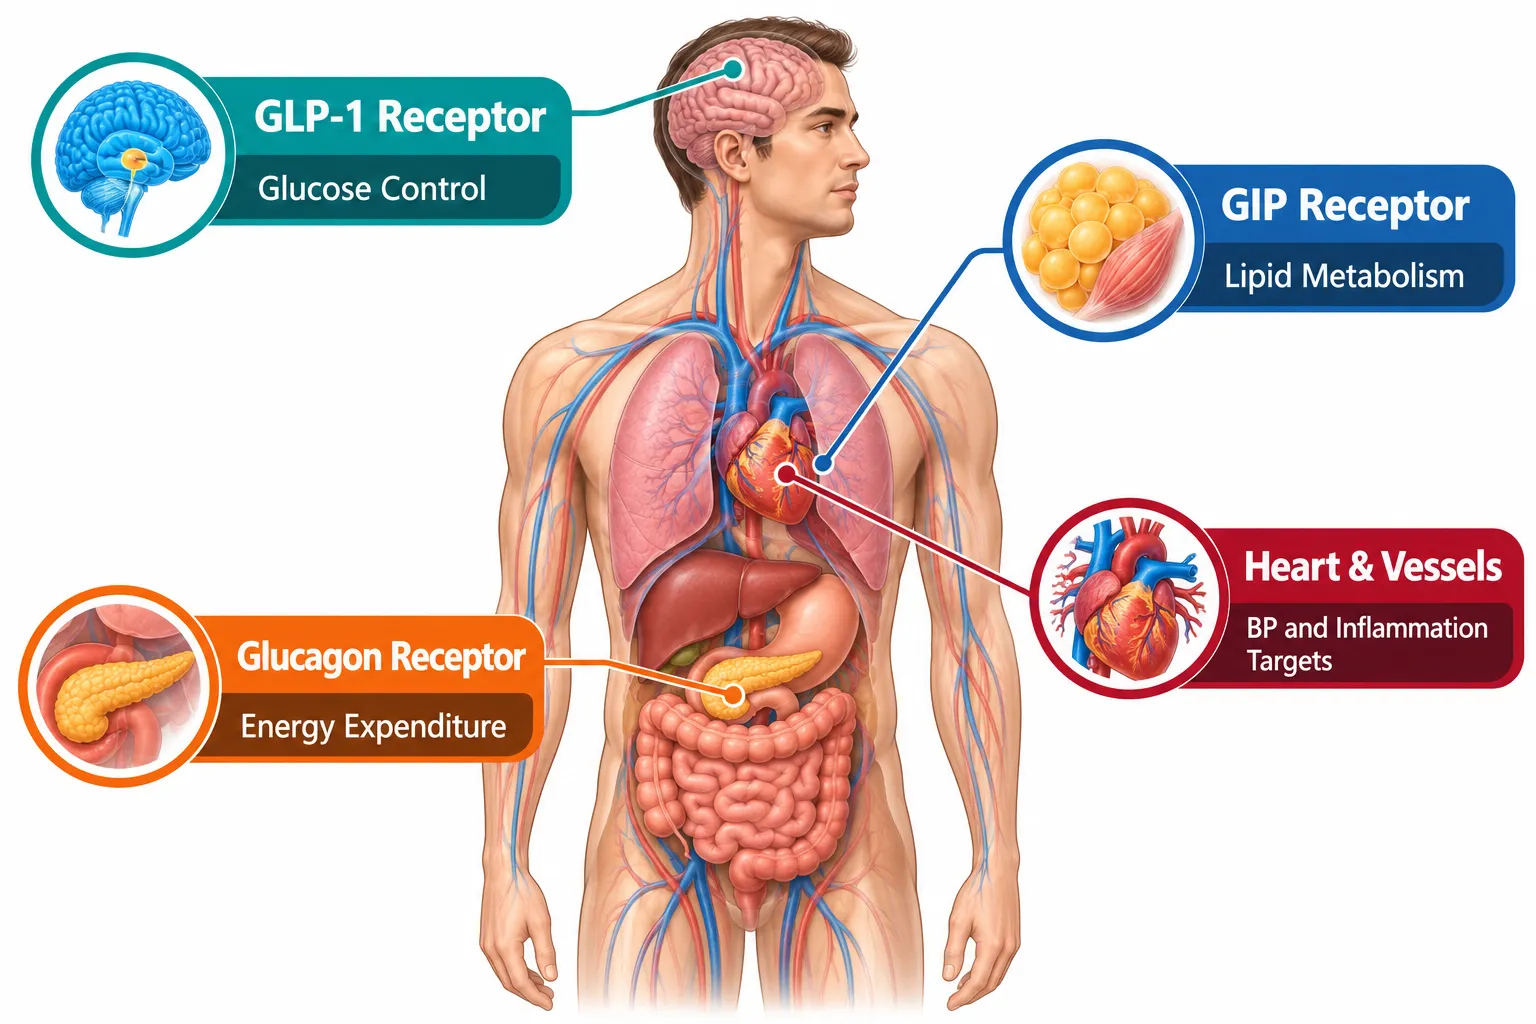
Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, a pharmacological profile that creates metabolic effects across multiple organ systems at once. This broad reach is precisely why retatrutide clinical trials have moved quickly to incorporate cardiometabolic measures as prespecified exploratory endpoints rather than afterthoughts.

In the pivotal phase 2 obesity trial published in the New England Journal of Medicine, once-weekly retatrutide produced a mean weight reduction of 24.2% at 48 weeks at higher doses. Alongside that headline figure, investigators tracked systolic and diastolic blood pressure, waist circumference, fasting glucose, insulin, glycated hemoglobin, and most lipid parameters. That multi-factor design reflected an early recognition that glucagon receptor agonism affects hepatic lipid metabolism and energy expenditure in ways that GLP-1 alone does not.

A 2024 meta-analysis confirmed statistically significant reductions in systolic blood pressure (pooled weighted mean difference of approximately -4.70 mmHg) and diastolic blood pressure (-1.73 mmHg) across retatrutide studies. Complementary Lancet data showed systolic blood pressure falling roughly 5 mmHg with active doses versus about 1.5 mmHg on placebo over 40 weeks. These consistent signals across studies support blood pressure as a reliable intermediate endpoint, one that is biologically plausible, measurable, and clinically meaningful.

Protocol planning note: Blood pressure and lipid changes are reproducible across retatrutide studies, making them strong candidates for secondary or co-primary endpoints in future trials. They should not be treated as incidental observations.

Researchers designing studies around GLP-1 Reta compounds increasingly recognize that a single surrogate endpoint misrepresents the drug's full cardiometabolic footprint.


Cardiometabolic Endpoint Design: From Signals to Evidence
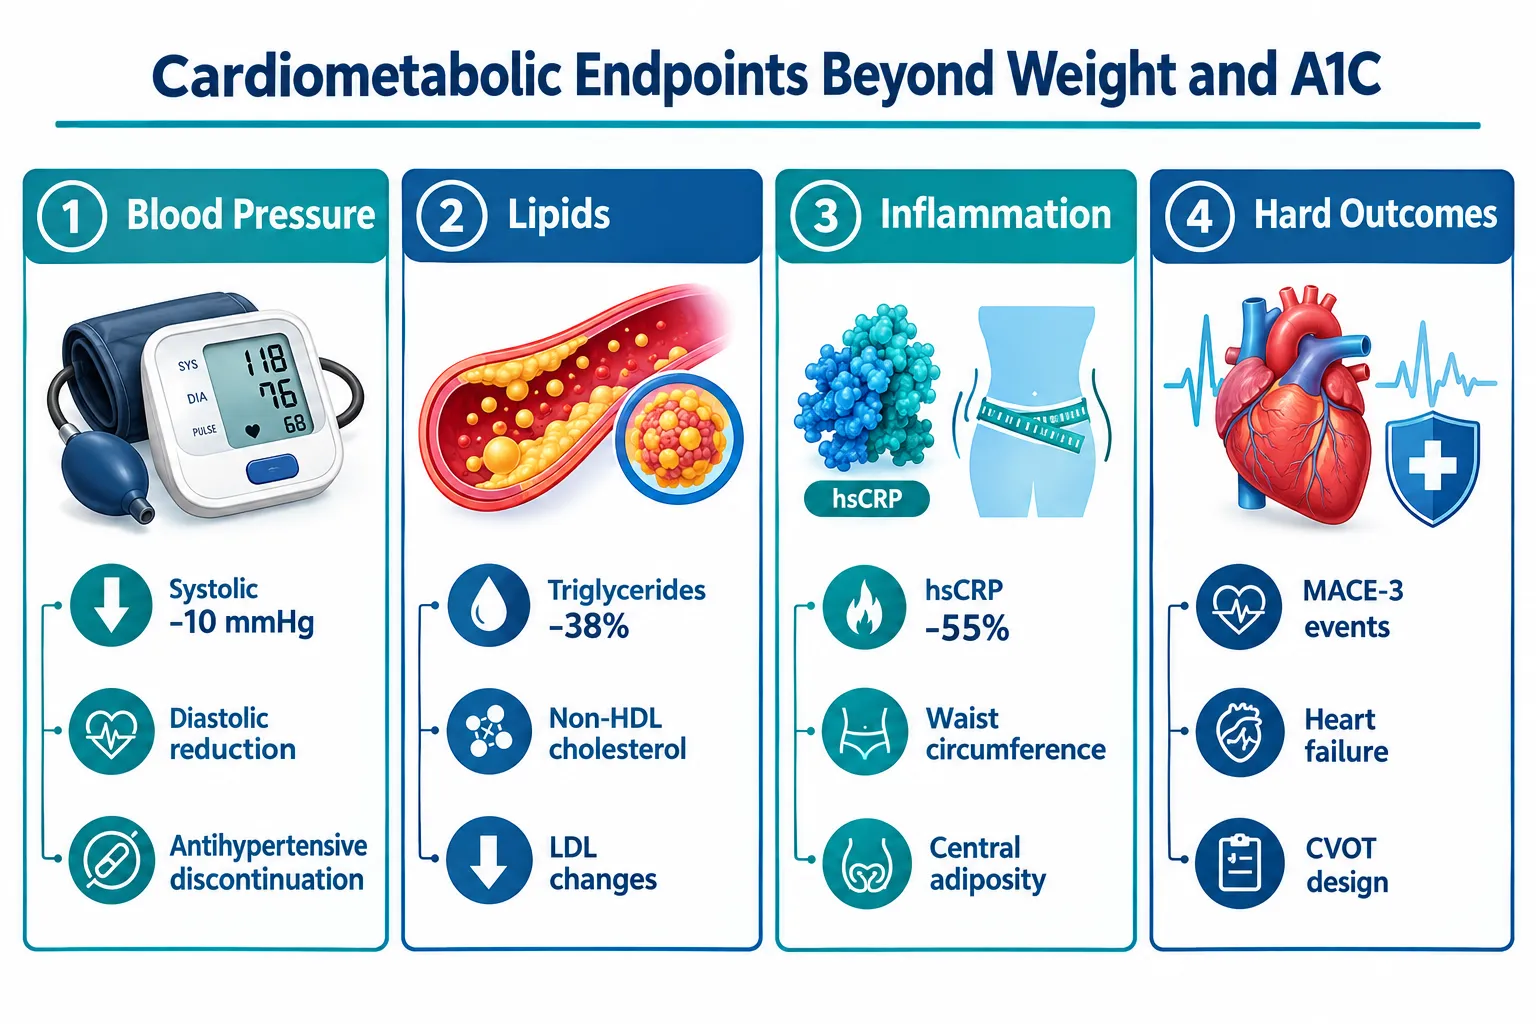
Cardiometabolic Endpoint Design: From Signals to Evidence

The TRIUMPH-3 phase 3 trial, which enrolled nearly 2,000 adults with severe obesity (BMI 35 or higher) and established cardiovascular disease, generated the most comprehensive cardiometabolic endpoint data to date. Results released in late September 2026 showed the following at the highest 12 mg dose:

Endpoint Approximate Change vs. Placebo
Systolic blood pressure -9.3 to -10.8 mmHg
Triglycerides -37 to -39.5%
Non-HDL cholesterol -16.5 to -19.6%
Waist circumference -16.9 to -19.0 cm
hsCRP -51 to -58%

These figures represent a multi-dimensional risk-modification profile that no single endpoint could capture. The hsCRP reduction in particular is notable: chronic low-grade inflammation is an independent cardiovascular risk factor, and a 51-58% drop in this marker suggests retatrutide may be modifying vascular biology beyond what weight loss alone would explain.

Equally important is the medication-burden signal. In the NEJM phase 2 trial, 41% of patients in the 8 mg group and 30% in the 12 mg group were able to discontinue at least one antihypertensive medication. This is a clinically relevant endpoint that regulatory agencies and payers increasingly value, it reflects real-world health impact, not just a surrogate number.

However, a critical distinction must be made. Despite these striking risk-factor improvements, TRIUMPH-3 did not show statistically significant reductions in major cardiovascular events. There were 44 MACE-5 events in the retatrutide group versus 52 in the placebo group, yielding a hazard ratio of 0.82 (95% CI 0.55-1.22). The MACE-3 hazard ratio was 1.12 (95% CI 0.64-1.96). The trial was not powered to detect event-level differences, and event counts were lower than projected. This is the essential gap between exploratory cardiometabolic signals and validated cardiovascular-outcome evidence.

For researchers working with related peptide frameworks such as SS-31 mitochondrial research or tesa dosage for fat loss protocols, this distinction between surrogate improvements and hard event outcomes is a recurring methodological challenge across the field.


Designing the Next Generation of Retatrutide Cardiovascular Endpoints

Designing the Next Generation of Retatrutide Cardiovascular Endpoints

A dedicated CVOT for retatrutide is now underway, targeting adults with overweight or obesity and established cardiovascular disease. This trial is explicitly designed to answer the question that TRIUMPH-3 could not: does retatrutide reduce major adverse cardiovascular events at a statistically powered level?

Recommended endpoint architecture for future retatrutide CVOTs:

  • Primary endpoint: MACE-3 (cardiovascular death, non-fatal myocardial infarction, non-fatal stroke) as the regulatory standard
  • Key secondary endpoints: Heart failure hospitalizations, kidney function trajectories, all-cause mortality
  • Exploratory biomarker endpoints: hsCRP, NT-proBNP, albuminuria, imaging-based myocardial structure measures
  • Safety hemodynamic monitoring: Pulse rate, arrhythmia surveillance, autonomic function, early diabetes studies showed increased pulse rate despite lower blood pressure, underscoring the need for comprehensive hemodynamic tracking

The inflammatory marker data from TRIUMPH-3 strengthens the case for including hsCRP and other inflammatory endpoints as prespecified secondary measures. A 51-58% reduction in hsCRP is not a minor signal; it warrants formal hypothesis testing in a powered trial.

Renal outcomes deserve explicit attention given the overlap between obesity, type 2 diabetes, and chronic kidney disease in high-risk populations. Albuminuria and estimated glomerular filtration rate trajectories should be incorporated as secondary endpoints, consistent with the approach taken in GLP-1 CVOT designs. For context on how related peptide research approaches multi-system endpoints, the GLP3 Reta compound research framework offers a useful parallel.

Lilly's March 2026 release on retatrutide in people with obesity and type 2 diabetes explicitly framed non-HDL cholesterol, triglyceride, and blood pressure improvements as key differentiating endpoints alongside glycemic control, signaling that the company's own endpoint strategy has already moved beyond weight and A1C.


Conclusion

Retatrutide and cardiovascular disease research is at a pivotal inflection point in 2026. The cardiometabolic signal is strong: blood pressure reductions of up to 10.8 mmHg, triglyceride drops approaching 40%, hsCRP reductions exceeding 50%, and clinically meaningful antihypertensive medication discontinuation rates all point to a drug with broad cardiovascular risk-modification potential.

What the evidence does not yet support is a validated claim of cardiovascular event reduction. TRIUMPH-3 was not powered for that conclusion, and the ongoing CVOT must deliver that answer before a formal cardiovascular risk-reduction indication can be pursued.

Actionable next steps for protocol designers and researchers:

  1. Build composite cardiometabolic endpoints into study designs from the start, do not treat blood pressure, lipids, and inflammation as secondary afterthoughts.
  2. Power dedicated CVOTs specifically for MACE, not just for weight loss, and include heart failure and renal outcomes as key secondary endpoints.
  3. Monitor hemodynamic safety comprehensively, including pulse rate and arrhythmia surveillance, given the mixed blood pressure and heart rate signals seen in early studies.
  4. Use inflammatory biomarkers such as hsCRP as prespecified exploratory endpoints to build the evidence base for future mechanistic claims.
  5. Follow retatrutide clinical trials progress closely, as CVOT results will determine whether the robust risk-factor improvements seen to date translate into the event-level cardiovascular benefit that patients and regulators require.

The science is compelling. The endpoint design must now match the ambition of the biology.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-and-cardiovascular-disease-research-designing-endpoints-beyond-weigh.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-03 13:04:482026-10-03 13:04:48Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C
Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together

Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together

September 26, 2026/0 Comments/in Uncategorized/by

Fewer than 40% of adults with severe obesity and established cardiovascular disease achieve meaningful, sustained weight loss through lifestyle intervention alone, yet researchers increasingly face a more complex challenge: determining whether the dramatic weight reductions produced by newer agents like retatrutide actually translate into reduced cardiovascular events, or whether they simply improve the numbers on a lab report.

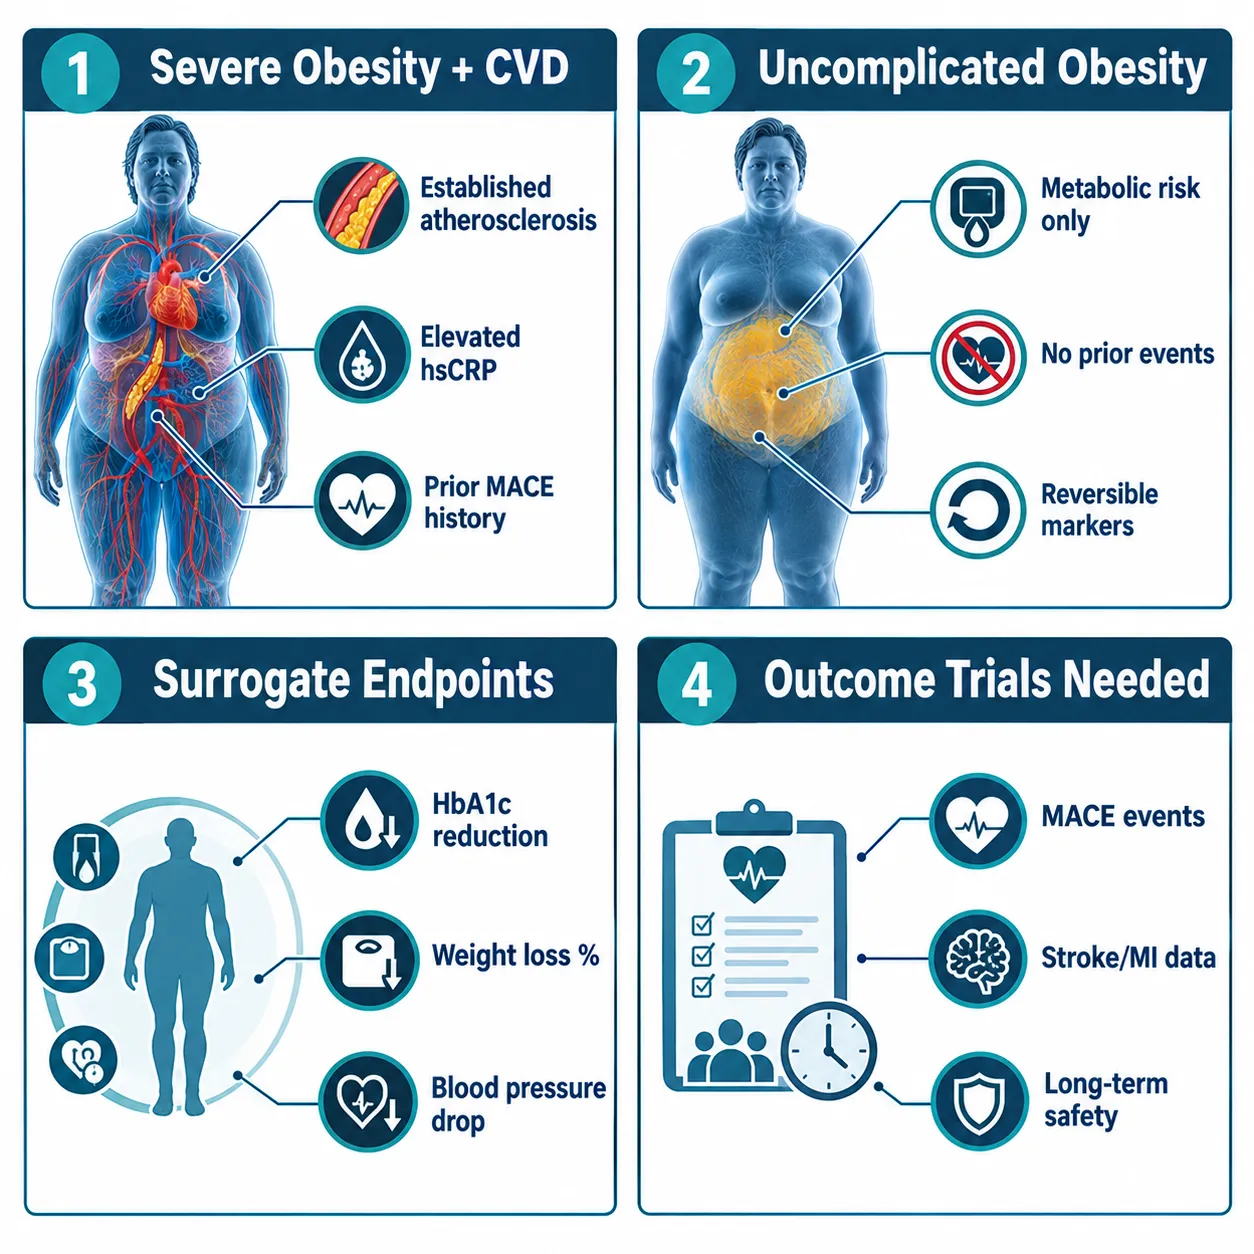
Retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together has become one of the most consequential methodological questions in metabolic medicine as of 2026. The drug's triple agonist mechanism, targeting GIP, GLP-1, and glucagon receptors simultaneously, produces weight loss that surpasses nearly every prior pharmacological benchmark. But the population most likely to receive this therapy in clinical practice is not the uncomplicated obesity cohort studied in pivotal trials. It is the patient with prior myocardial infarction, heart failure, or advanced atherosclerosis, where surrogate endpoints and actual cardiovascular outcomes can diverge sharply.

Key Takeaways

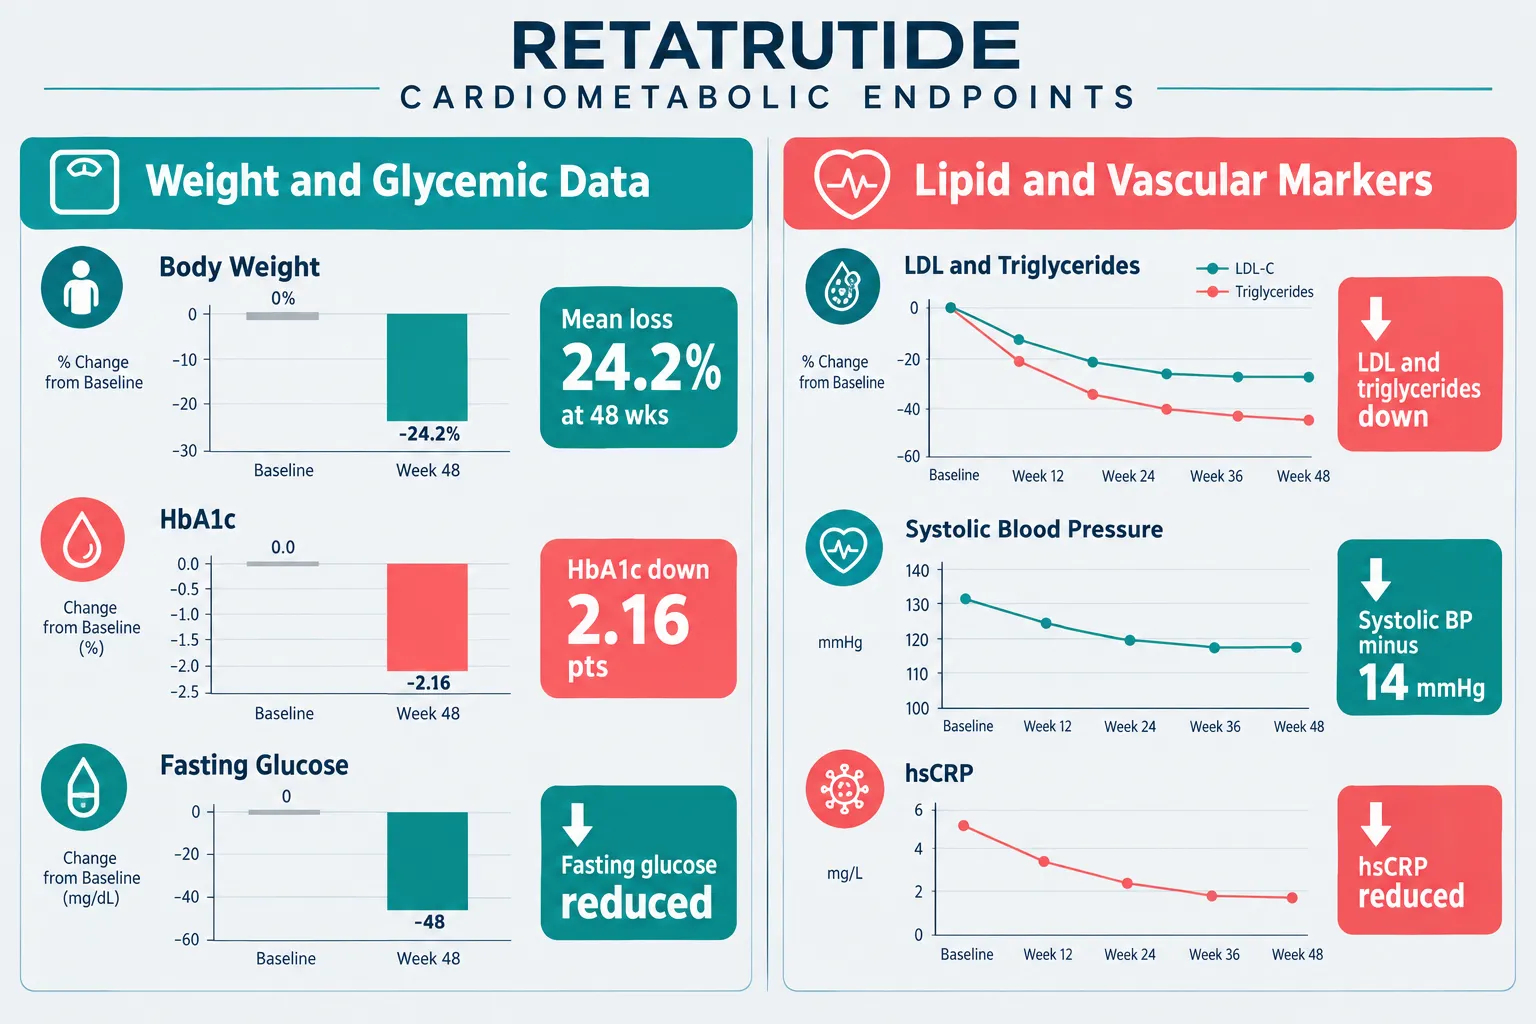
  • Retatrutide produced mean body weight reductions of up to 24.2% at 48 weeks in phase 2 trials, exceeding prior pharmacological benchmarks.
  • Glycemic improvements, including HbA1c reductions of approximately 2.16 percentage points, occurred alongside weight loss in both diabetic and non-diabetic populations.
  • Lipid panels, blood pressure, and inflammatory markers all shifted in a cardiovascular-favorable direction, but these remain surrogate endpoints.
  • No completed cardiovascular outcomes trials have yet confirmed reductions in major adverse cardiovascular events (MACE) for retatrutide.
  • Researchers must resist treating weight loss as a direct proxy for cardiovascular benefit, particularly in high-risk populations with established disease.

Why the Severe-Obesity CVD Population Demands a Different Analytical Frame

Why the Severe-Obesity CVD Population Demands a Different Analytical Frame

The distinction between uncomplicated obesity and obesity complicated by established cardiovascular disease is not semantic, it is mechanistically and statistically critical. In uncomplicated obesity cohorts, cardiovascular risk is largely driven by modifiable metabolic factors: insulin resistance, dyslipidemia, and hypertension. Meaningful weight loss reliably improves these factors, and the pathway from surrogate improvement to event reduction is relatively well-supported by prior evidence from bariatric surgery and GLP-1 receptor agonist outcomes trials.

In the severe-obesity CVD population, however, the risk architecture is different. Atherosclerotic plaques are already established. Inflammatory burden is higher. Cardiac remodeling may be present. The relationship between short-term biomarker improvement and long-term event reduction is less predictable, and the potential for adverse interactions, including changes in heart rate, volume shifts from rapid weight loss, or arrhythmia risk, requires independent evaluation rather than inference from surrogate data.

This is the central interpretive challenge for retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together requires researchers to resist collapsing a multi-dimensional risk picture into a single headline number.

Researchers reviewing retatrutide endpoints data should note that the phase 2 obesity trial enrolled adults without diabetes and without prior cardiovascular events. Extrapolating those results to a post-MI population with preserved or reduced ejection fraction introduces assumptions that the data do not yet support.


What the Phase 2 Data Actually Show: Weight, Glycemic, and Lipid Endpoints

What the Phase 2 Data Actually Show: Weight, Glycemic, and Lipid Endpoints

The phase 2 evidence base for retatrutide is genuinely impressive across multiple dimensions. In the pivotal obesity trial involving 338 adults, once-weekly retatrutide at 12 mg produced a mean body weight reduction of 24.2% at 48 weeks. The 8 mg dose achieved 22.8% mean loss. Placebo-adjusted weight reduction at 24 weeks was approximately 16%, with a continued downward trajectory through the trial period. Every participant receiving 8 or 12 mg weekly achieved at least 5% weight loss, a threshold widely cited in regulatory and guideline contexts as clinically meaningful for cardiovascular risk.

Glycemic endpoints reinforced the cardiometabolic signal. In a separate 36-week phase 2 study in adults with type 2 diabetes, the highest dose produced an average HbA1c decrease of approximately 2.16 percentage points alongside up to 16.9% weight reduction. Fasting glucose and fasting insulin also declined in parallel with weight loss in the obesity trial.

Key insight: A 2.16 percentage-point HbA1c reduction in a population with established type 2 diabetes is clinically substantial, but it is a surrogate marker for cardiovascular risk, not a direct measure of event prevention.

Lipid and inflammatory markers moved in favorable directions. Triglycerides, LDL cholesterol, non-HDL cholesterol, and total cholesterol all declined. HDL modestly improved. Systolic blood pressure fell by roughly 4-8 mmHg across effective dose arms in the obesity trial, and by approximately 14 mmHg at the highest dose in a manufacturer-reported analysis using an efficacy estimand. High-sensitivity C-reactive protein (hsCRP), a marker of systemic inflammation strongly associated with cardiovascular events, was also reduced.

Waist circumference decreased by approximately 10-15 cm across effective dose arms, a change relevant to visceral adiposity and its downstream effects on insulin sensitivity and hepatic lipid metabolism.

For researchers seeking GLP-3 Reta 30mg formulations for preclinical or translational research purposes, these multi-endpoint findings provide a rich framework for designing studies that go beyond single-biomarker outcomes.


Interpreting Safety Endpoints Alongside Efficacy: What Researchers Must Not Overlook

Interpreting Safety Endpoints Alongside Efficacy: What Researchers Must Not Overlook

Safety data from phase 2 trials show a profile broadly consistent with potent incretin-based therapies. Adverse events were predominantly gastrointestinal, nausea, vomiting, and diarrhea, and were more frequent at higher doses, consistent with dose-dependent receptor engagement. Serious adverse events were infrequent, and the overall safety profile was considered acceptable for continued development.

Critically, available phase 2 summaries do not signal major cardiovascular safety concerns over 36-48 weeks. But this observation carries an important caveat: 36-48 weeks is insufficient to characterize arrhythmia risk, heart failure decompensation risk, or ischemic event rates in a population with established cardiovascular disease.

Researchers must treat the absence of a safety signal as a starting point for investigation, not a conclusion.

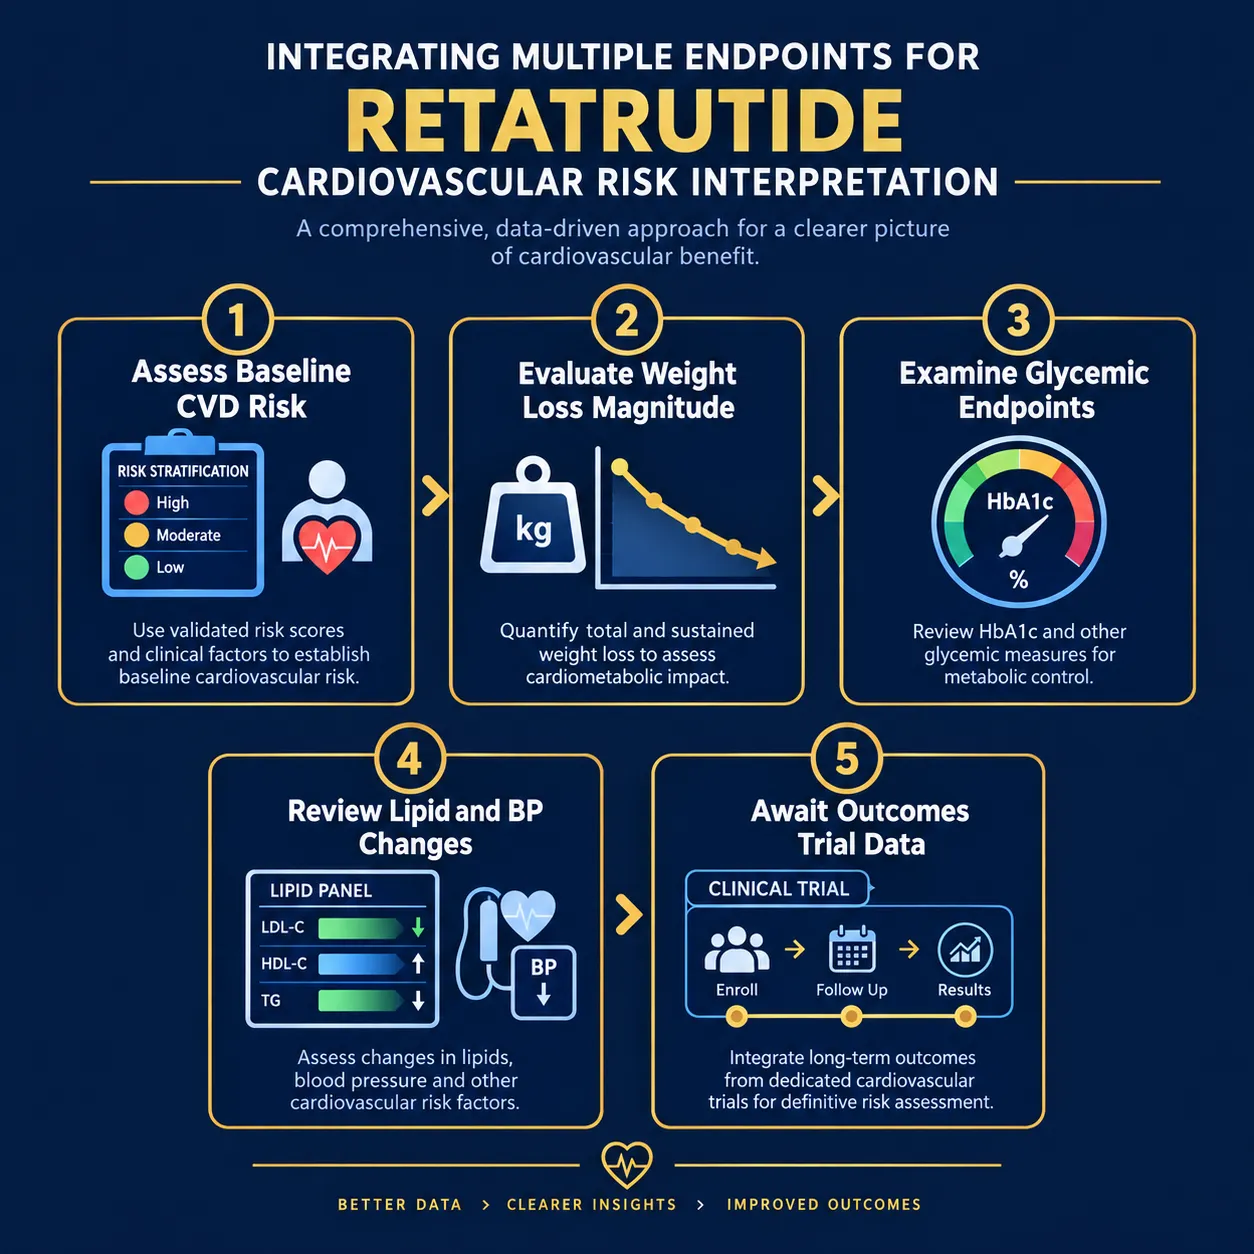
The integrated interpretation framework for retatrutide and cardiovascular disease research, interpreting weight, glycemic, and safety endpoints together, should follow a structured logic:

  1. Stratify baseline cardiovascular risk before interpreting any endpoint change.
  2. Evaluate weight loss magnitude in the context of rate and composition, not just percentage.
  3. Examine glycemic endpoints as independent contributors to risk, not simply as weight-loss correlates.
  4. Review lipid and blood pressure changes with attention to clinical significance thresholds.
  5. Identify gaps: no completed MACE outcomes trial exists for retatrutide as of 2026.

Researchers exploring adjacent cardiometabolic peptide research, including SS-31 kidney health research, will recognize this multi-endpoint interpretive discipline as standard practice in high-risk populations where organ-level interactions are complex.

Those sourcing compounds for translational research can review available Reta 20mg for sale options or GLP-3 Reta CAG 10mg for sale formulations through verified research-grade suppliers.


Conclusion

The surrogate endpoint data for retatrutide are among the most compelling seen in pharmacological obesity research. Weight loss of 24% at 48 weeks, combined with substantial HbA1c reduction, improved lipid panels, lower blood pressure, and reduced hsCRP, constructs a plausible and mechanistically coherent case for cardiovascular benefit.

But plausibility is not proof, particularly in the severe-obesity cardiovascular disease population where the stakes are highest and the biology is most complex.

Actionable next steps for researchers and clinicians:

  • Design studies that explicitly enroll patients with established cardiovascular disease, not just metabolic risk factors.
  • Pre-specify cardiovascular safety endpoints, including arrhythmia monitoring and heart failure hospitalization, as primary or co-primary outcomes, not secondary analyses.
  • Avoid reporting weight loss as a cardiovascular outcome; report it as one component of a multi-endpoint risk profile.
  • Track cardiovascular outcomes trial timelines for retatrutide and resist extrapolating event-level benefit from surrogate data until those trials report.
  • When reviewing buy Reta online options for preclinical research, ensure purity and dosing specifications align with the phase 2 protocols to maintain translational relevance.

The science surrounding retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together is advancing rapidly. The discipline required to interpret that science rigorously, especially in high-risk populations, must advance at the same pace.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-and-cardiovascular-disease-research-interpreting-weight-glycemic-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:11:232026-09-26 13:11:23Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top