Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: finasteride

Finasteride and Enclomiphene in Hormone Research: Interpreting DHT, Testosterone, LH, and FSH Together

Finasteride and Enclomiphene in Hormone Research: Interpreting DHT, Testosterone, LH, and FSH Together

November 3, 2026/0 Comments/in Uncategorized/by

Two drugs. Four hormones. Entirely different mechanisms, yet both elevate circulating testosterone. That distinction is exactly why finasteride and enclomiphene in hormone research interpreting DHT, testosterone, LH, and FSH together demands a coordinated panel framework rather than a single-marker read. When researchers examine only total testosterone, they miss the mechanistic story written across the full endocrine axis.

Key Takeaways

  • Enclomiphene stimulates the hypothalamic-pituitary axis, producing elevated testosterone alongside elevated LH and FSH, a classic axis-driven signature.
  • Finasteride suppresses DHT by roughly 65% while leaving LH and FSH largely unchanged, indicating peripheral androgen conversion inhibition rather than axis stimulation.
  • Interpreting testosterone alone is insufficient; DHT, LH, and FSH must be measured simultaneously to distinguish these two mechanisms.
  • Timing matters: enclomiphene's gonadotropin effects are measurable within 4-6 weeks, while finasteride's DHT suppression occurs within 24 hours of dosing.
  • The combined hormone profile also informs fertility considerations: enclomiphene preserves or improves semen parameters, while finasteride's fertility-related risks appear mediated by intratesticular pathways rather than gross gonadotropin shifts.

How Each Compound Acts on the Endocrine Axis
How Each Compound Acts on the Endocrine Axis

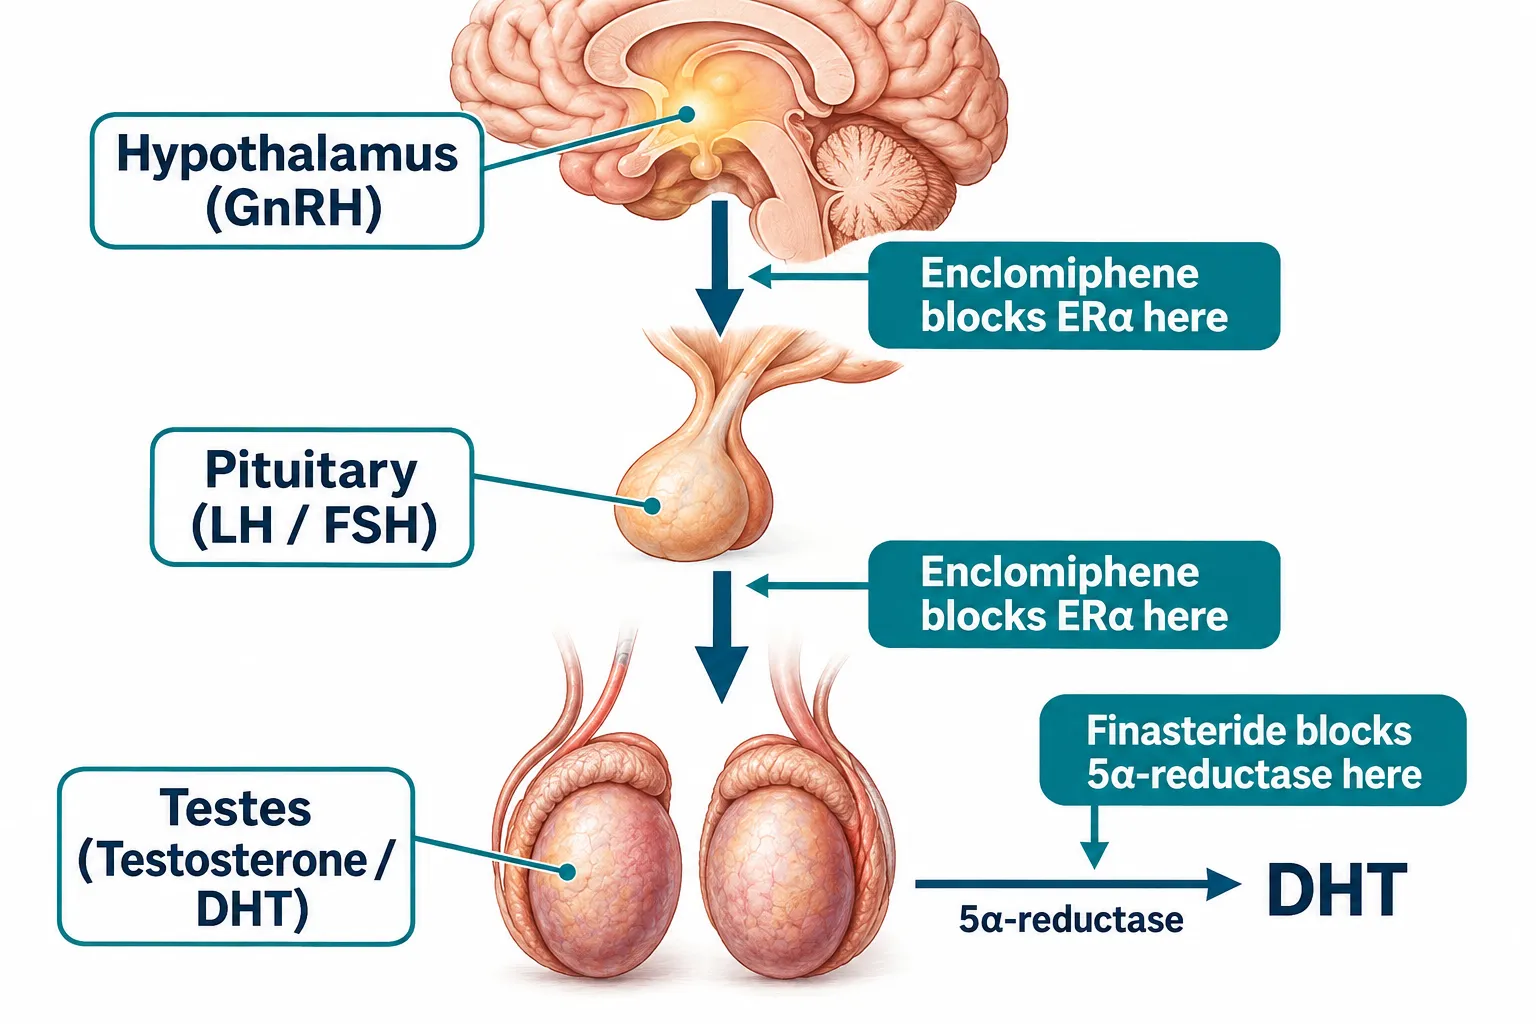
Understanding the biology behind finasteride and enclomiphene in hormone research, interpreting DHT, testosterone, LH, and FSH together, begins at the receptor level.

Enclomiphene is the trans-isomer of clomiphene. It antagonizes estrogen receptors (ERα) in hypothalamic neurons and pituitary gonadotrophs, blocking the negative-feedback signal that estrogen normally sends to suppress GnRH pulsatility. The result is a cascade: GnRH rises, stimulating the pituitary to release more LH and FSH, which in turn drive the testes to produce more testosterone and support spermatogenesis. This is axis stimulation from the top down.

Finasteride works entirely differently. It inhibits 5-alpha-reductase, the enzyme that converts testosterone into dihydrotestosterone (DHT) in peripheral tissues. It does not touch the hypothalamus or pituitary directly. DHT falls sharply; testosterone edges upward modestly as a compensatory response; the gonadotropin axis remains largely intact.

"Elevated testosterone with elevated LH and FSH points to serm-mediated axis stimulation. Elevated testosterone with suppressed DHT and stable gonadotropins points to 5-alpha-reductase inhibition. The pattern tells the story."

These contrasting mechanisms explain why a full hormone panel, not testosterone alone, is the only reliable interpretive tool in research involving either compound.


Characteristic Hormone Signatures: What the Data Show
Characteristic Hormone Signatures: What the Data Show

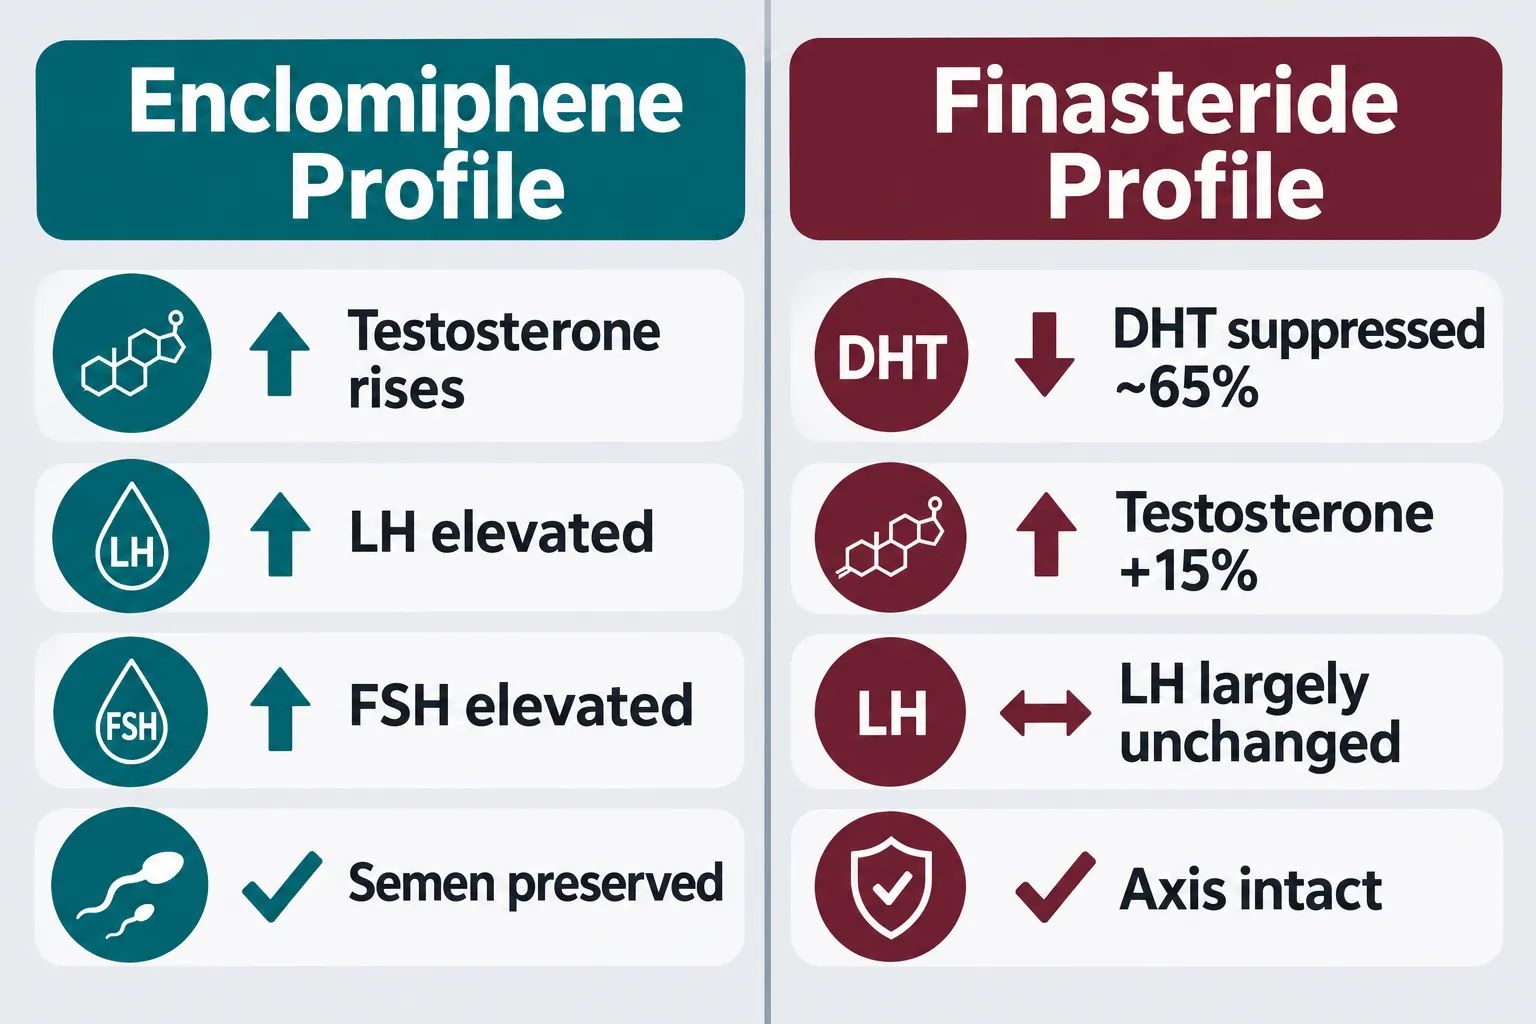
Across multiple controlled trials and systematic reviews, a consistent set of laboratory signatures has emerged for each compound.

Enclomiphene Hormone Profile

In a large meta-analysis of serm therapy in functional male hypogonadism, treatment produced a mean testosterone increase of approximately 274 ng/dL versus placebo. Crucially, LH rose by roughly 4.7 IU/L and FSH by approximately 4.6 IU/L, both statistically significant. In a direct comparison with transdermal testosterone, daily enclomiphene achieved non-inferior testosterone levels at both 24 hours and 6 weeks while maintaining physiological gonadotropin secretion rather than suppressing it.

A 2016 randomized trial illustrated the pattern precisely. Men on 25 mg enclomiphene saw LH rise from 5.3 to 11.9 mIU/mL and FSH from 9.4 to 14.9 mIU/mL. Men on exogenous testosterone saw LH fall from 3.9 to 1.4 mIU/mL and FSH from 6.0 to 2.4 mIU/mL, a textbook axis-suppression profile. Approximately 68% of hypogonadal men on enclomiphene achieved physiologic testosterone levels of 450-650 ng/dL without broad axis suppression.

Enclomiphene expected panel pattern:

Hormone Direction
Total Testosterone Significantly elevated
LH Significantly elevated
FSH Significantly elevated
DHT Unchanged or mildly reduced
Semen parameters Preserved or improved

Finasteride Hormone Profile

Finasteride presents a strikingly different signature. Serum DHT is suppressed by approximately 65% within 24 hours of a 1 mg oral dose. Testosterone increases by roughly 10-20%, remaining within the physiological range. In most healthy men, LH and FSH show little to no meaningful change; the hypothalamic-pituitary-testicular axis continues functioning normally. Classic volunteer studies using 5 mg/day finasteride confirmed no significant changes in basal or GnRH-stimulated LH and FSH despite near-complete DHT suppression.

One exception worth noting: in older men with benign prostatic hyperplasia treated for three months, FSH and LH showed modest decreases of roughly 24% and 16%, respectively. This context-dependence reinforces why interpreting hormone panels requires clinical framing, not just reference ranges.

Finasteride expected panel pattern:

Hormone Direction
DHT Suppressed ~65%
Total Testosterone Mildly elevated (+10-20%)
LH Largely unchanged (minor increase or decrease)
FSH Largely unchanged
Semen parameters Systemic hormones unaffected; intratesticular risks possible

A Practical Framework for Interpreting Combined Panels
A Practical Framework for Interpreting Combined Panels

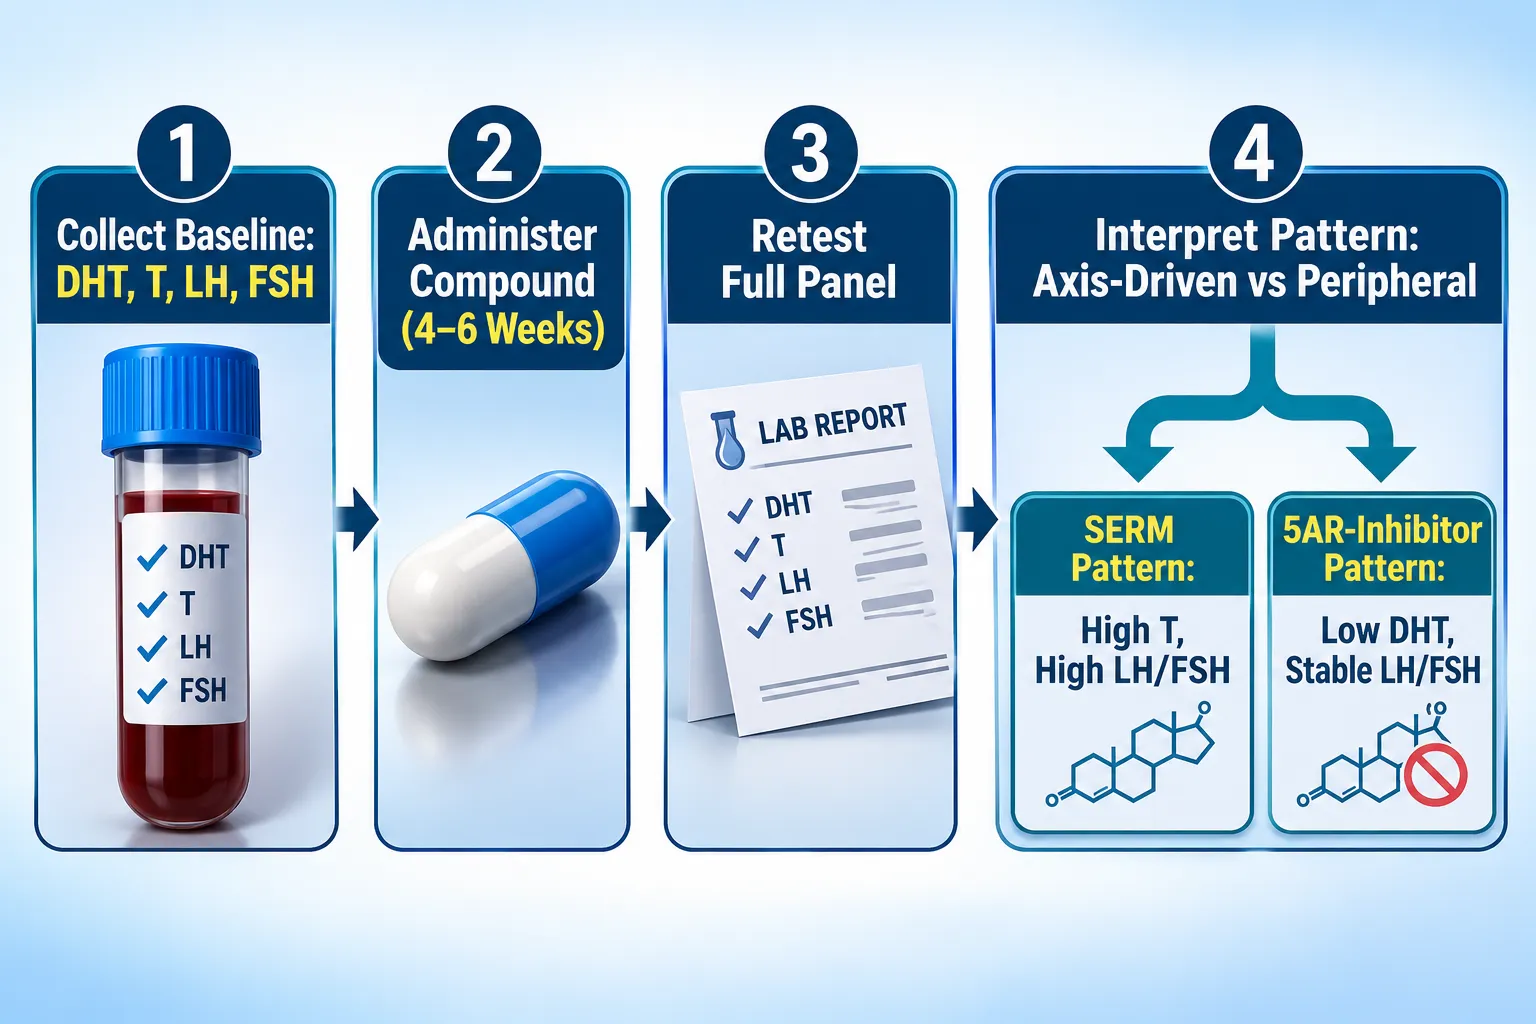
Applying the principles of finasteride and enclomiphene in hormone research, interpreting DHT, testosterone, LH, and FSH together, calls for a structured, timing-aware approach.

Step 1: Establish a True Baseline

Collect fasting morning DHT, total testosterone, free testosterone, LH, and FSH before any compound is introduced. Baseline LH and FSH stratification is especially important because it distinguishes primary hypogonadism (high LH/FSH) from secondary hypogonadism (low or normal LH/FSH), which determines whether serm therapy is appropriate.

Step 2: Apply Compound-Specific Timing Windows

  • Finasteride: DHT suppression begins within 24 hours. Stable new-state DHT is typically observed by day 14-28.
  • Enclomiphene: Gonadotropin elevation begins within days, but the full testosterone response generally matures over 4-6 weeks. Assess the complete panel at the 4-6 week mark for a reliable read.

Step 3: Interpret the Full Pattern, Not Individual Values

A testosterone value of 550 ng/dL carries entirely different implications depending on what accompanies it:

  • 550 ng/dL T + LH 10 mIU/mL + FSH 12 mIU/mL + normal DHT = enclomiphene-type axis stimulation
  • 550 ng/dL T + LH 1.5 mIU/mL + FSH 2.0 mIU/mL + normal DHT = exogenous testosterone or axis-suppressive therapy
  • 550 ng/dL T + LH stable + FSH stable + DHT 0.17 ng/mL = finasteride-type peripheral conversion inhibition

Step 4: Integrate Fertility-Relevant Markers

When reproductive outcomes matter, add semen analysis. serm therapy with enclomiphene consistently maintains or improves semen parameters, a key differentiator from exogenous testosterone. Finasteride's gonadotropin profile appears essentially unchanged in healthy men, but intratesticular DHT changes may affect fertility through pathways not visible in standard serum panels.

For researchers sourcing comparison compounds, reviewing peptide supplier comparisons and interpreting catalog sources can help ensure compound integrity when building multi-arm research protocols. Those designing broader hormonal studies may also find value in reviewing GLP-1 peptide generational research concepts and sourcing notes for adjacent metabolic endpoints. Similarly, researchers examining mitochondrial and metabolic co-factors alongside hormonal readouts can reference SS-31 mitochondrial research for context on oxidative-stress markers that may interact with androgen signaling. For studies requiring precise compound storage and traceability practices, the notes in AOD-9604 sale research method notes, storage, and traceability offer transferable guidance. Researchers pairing growth-hormone secretagogues with hormonal panels may also consult can you take Ipamorelin and CJC-1295 together for multi-compound interaction considerations.


Conclusion

The core lesson from current research is straightforward: testosterone alone cannot differentiate between serm-mediated endocrine feedback and 5-alpha-reductase inhibition. The full pattern, DHT suppressed or intact, LH and FSH elevated or stable, semen parameters preserved or not, is the only reliable interpretive framework when examining finasteride and enclomiphene in hormone research interpreting DHT, testosterone, LH, and FSH together.

Actionable next steps for researchers:

  1. Always collect a four-hormone baseline (DHT, total T, LH, FSH) before introducing either compound.
  2. Apply compound-specific timing windows, 24-28 days for finasteride's DHT nadir; 4-6 weeks for enclomiphene's full gonadotropin and testosterone response.
  3. Read patterns, not values, the hormonal signature, not any single number, identifies the mechanism at work.
  4. Add semen analysis when fertility outcomes are a research endpoint.
  5. Stratify by baseline gonadotropin status to contextualize serm response appropriately.

Following this framework turns a standard hormone panel into a mechanistically informative research tool, one capable of distinguishing axis stimulation from peripheral androgen modulation with precision.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/finasteride-and-enclomiphene-in-hormone-research-interpreting-dht-testosterone-l.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-03 14:06:012026-11-03 14:06:01Finasteride and Enclomiphene in Hormone Research: Interpreting DHT, Testosterone, LH, and FSH Together
Best Research-Grade Hair Follicle and Tissue Compounds: Finasteride vs. GHK-Cu and Copper Peptide Formulations

Best Research-Grade Hair Follicle and Tissue Compounds: Finasteride vs. GHK-Cu and Copper Peptide Formulations

September 17, 2026/0 Comments/in Uncategorized/by

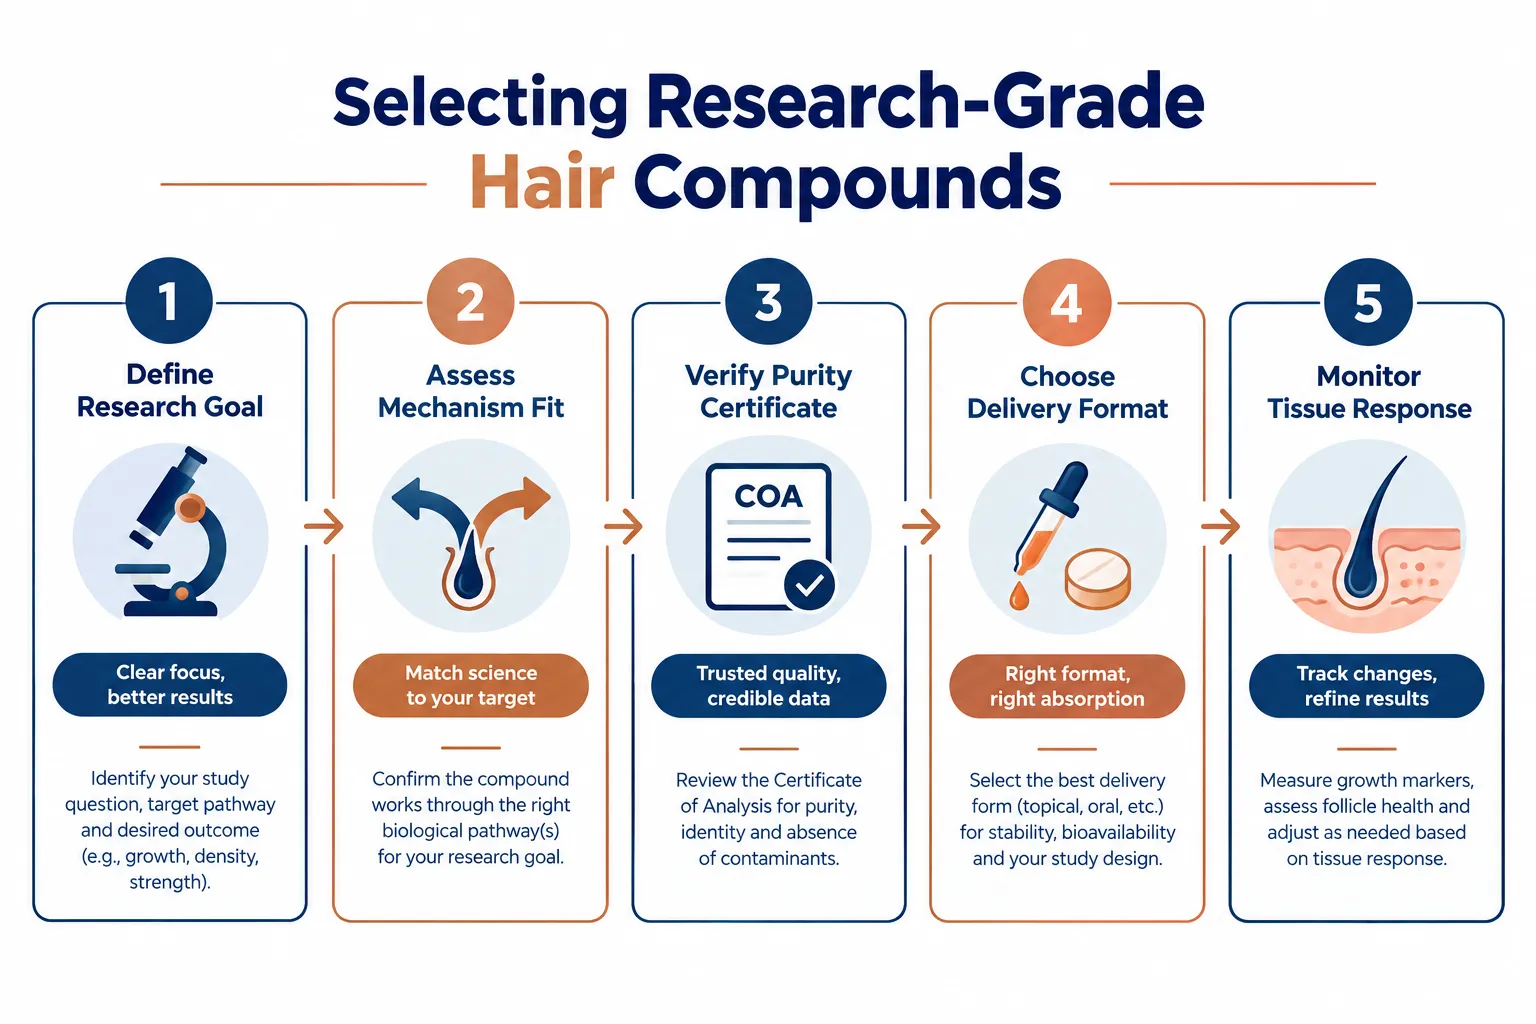
Androgenetic alopecia affects roughly 50% of men by age 50 and a significant proportion of women across all age groups, yet the two most studied compound classes in hair follicle research operate through entirely different biological mechanisms. When evaluating the best research-grade hair follicle and tissue compounds, finasteride vs. GHK-Cu and copper peptide formulations, the central question is not simply which compound works, but which mechanism matches a given research objective.

Key Takeaways

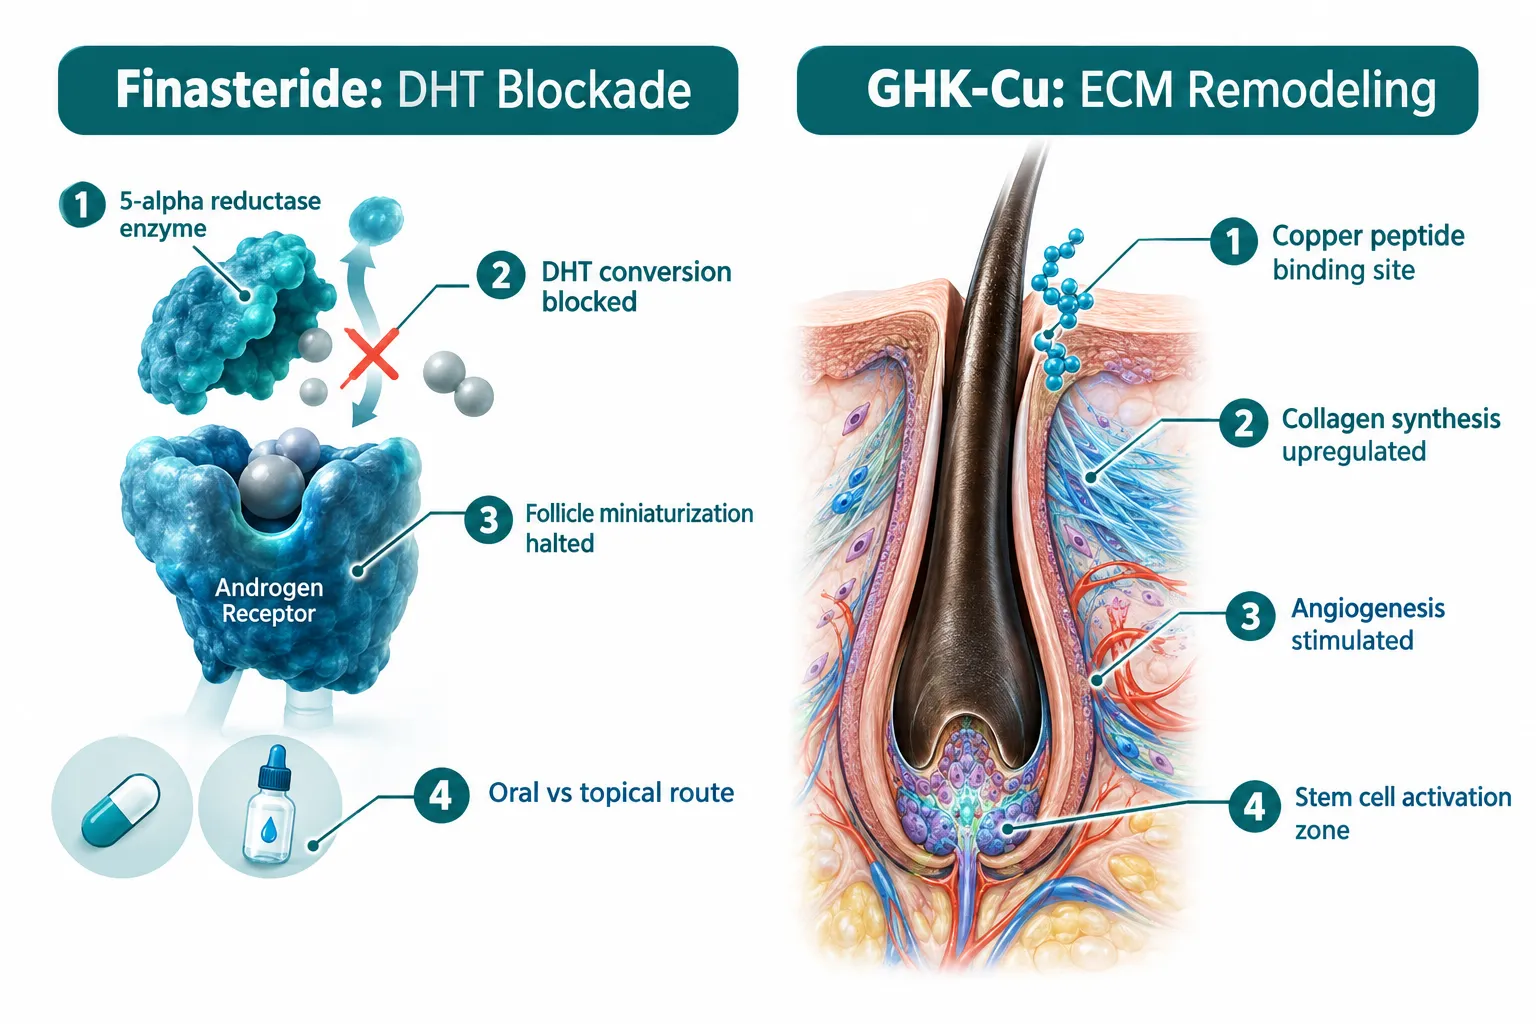
  • Finasteride blocks dihydrotestosterone (DHT) synthesis by inhibiting 5-alpha reductase, directly addressing androgen-driven follicle miniaturization.
  • GHK-Cu (glycine-histidine-lysine copper complex) promotes extracellular matrix remodeling, angiogenesis, and stem cell signaling in follicular tissue.
  • Topical finasteride formulations show substantially reduced systemic absorption compared to oral routes, improving the safety profile in research models.
  • Copper peptides are classified as research-grade compounds with no current clinical approval for hair loss, placing them in a distinct regulatory category from finasteride.
  • Combination approaches targeting both androgen pathways and tissue remodeling represent an emerging area of preclinical investigation.

How Finasteride Targets DHT in Hair Follicle Research

How Finasteride Targets DHT in Hair Follicle Research

Finasteride is a synthetic 4-azasteroid that competitively inhibits type II 5-alpha reductase, the enzyme responsible for converting testosterone into dihydrotestosterone. DHT binds to androgen receptors within dermal papilla cells, triggering a cascade that progressively miniaturizes hair follicles. By reducing scalp DHT levels by approximately 60-70%, finasteride interrupts this process at the enzymatic source.

Oral vs. topical delivery represents a critical variable in research design:

  • Oral finasteride (1 mg daily): Achieves systemic DHT suppression; well-documented in large cohort studies over decades.
  • Topical finasteride (0.25% solution): Demonstrates localized scalp DHT reduction with significantly lower plasma concentrations, reducing the risk of systemic side effects including sexual dysfunction.

A large telehealth cohort analysis confirmed that compounded topical finasteride produces meaningful hair density improvements comparable to oral dosing, while network meta-analyses position it favorably among off-label androgenetic alopecia therapies. Combination formulations pairing topical finasteride with minoxidil consistently outperform minoxidil alone across both real-world data and controlled trials.

"The route of administration is not a minor detail, it fundamentally changes the systemic exposure profile and the risk-benefit calculation for any research model."

Safety considerations remain relevant. Sexual dysfunction, including decreased libido and erectile changes, has been documented with oral 5-alpha reductase inhibitors. Topical routes reduce but do not fully eliminate this concern. Dutasteride, which inhibits both type I and type II isoforms, produces deeper DHT suppression but carries a broader systemic footprint than finasteride in comparative studies.

GHK-Cu and Copper Peptide Formulations: Tissue Remodeling Mechanisms

GHK-Cu and Copper Peptide Formulations: Tissue Remodeling Mechanisms

GHK-Cu (glycyl-L-histidyl-L-lysine copper II) is a naturally occurring tripeptide-copper complex first isolated from human plasma. Unlike finasteride, it does not interfere with androgen signaling. Instead, it operates through extracellular matrix (ECM) remodeling, angiogenesis stimulation, and activation of follicular stem cell niches.

Key biological activities documented in preclinical research include:

  • Collagen and glycosaminoglycan synthesis: GHK-Cu upregulates genes involved in ECM production, improving the structural environment surrounding the follicle.
  • Angiogenesis: The compound promotes vascular endothelial growth factor (VEGF) expression, increasing blood supply to the dermal papilla.
  • Anti-inflammatory signaling: Copper peptides modulate inflammatory cytokines that can accelerate follicle cycling disruption.
  • Stem cell activation: Preclinical data suggest GHK-Cu may influence hair follicle stem cell populations in the bulge region.

For researchers sourcing compounds, verified purity is non-negotiable. Resources such as the guide on where to buy research-grade Glow Blend peptide: evaluating purity, copper complexes, and skin model compatibility provide practical frameworks for assessing copper peptide formulations. Similarly, researchers exploring tissue repair models may find value in reviewing wound healing peptide applications, as GHK-Cu's ECM activity overlaps with dermal wound healing pathways.

Those sourcing copper peptide compounds for follicle studies should verify certificate of analysis (COA) data confirming greater than 98% purity, absence of endotoxins, and accurate copper chelation ratios. Options for GHK-Cu peptide for sale from tested suppliers offer a starting point for procurement research.

Comparing Research-Grade Compounds: Finasteride vs. GHK-Cu Side by Side

Comparing Research-Grade Compounds: Finasteride vs. GHK-Cu Side by Side

When selecting the best research-grade hair follicle and tissue compounds, finasteride vs. GHK-Cu and copper peptide formulations, researchers must align compound choice with the specific biological question being investigated.

Feature Finasteride GHK-Cu / Copper Peptides
Primary mechanism 5-alpha reductase inhibition / DHT blockade ECM remodeling, angiogenesis, stem cell signaling
Regulatory status FDA-approved (oral); compounded topical off-label Research-grade only; no clinical approval for AGA
Systemic exposure risk Moderate (oral); low (topical) Minimal with topical application
Best research use Androgen-driven follicle miniaturization models Tissue repair, follicle cycling, vascularization models
Combination potential Strong with minoxidil; speculative with GHK-Cu Speculative with finasteride; explored with [wound healing peptides](https://www.puretestedpeptides.com/tag/wound-healing-peptides/)

Regulatory distinction matters. Finasteride has an established clinical approval history, whereas copper peptide formulations remain in the research-compound category. This affects sourcing standards, documentation requirements, and permissible research contexts. Researchers working with GHK-Cu peptides for sale should maintain rigorous documentation of compound provenance and purity.

Combination Research Models

Preclinical interest is growing in dual-mechanism approaches. The rationale: finasteride addresses the androgen-driven cause of follicle miniaturization, while GHK-Cu supports the tissue environment needed for follicle recovery. No peer-reviewed clinical trial has yet validated this combination in humans, and any such application remains speculative. Researchers exploring multi-peptide tissue models may also find mechanistic parallels in wound healing peptides literature, given the overlapping ECM pathways.

Conclusion

The best research-grade hair follicle and tissue compounds, finasteride vs. GHK-Cu and copper peptide formulations, are not competitors in the conventional sense. They occupy different mechanistic niches. Finasteride is the established standard for DHT-suppression models, with robust long-term data supporting both oral and topical routes. GHK-Cu offers a distinct research avenue focused on ECM remodeling and angiogenesis, with promising preclinical data but no clinical approval for androgenetic alopecia.

Actionable next steps for researchers:

  1. Define the primary research question: androgen pathway inhibition or tissue microenvironment support.
  2. Select compounds from suppliers providing COA documentation, endotoxin testing, and verified purity above 98%.
  3. For finasteride models, evaluate topical formulations to minimize systemic confounders.
  4. For copper peptide models, cross-reference with ECM and wound healing literature to build mechanistic context.
  5. Treat combination models as exploratory and clearly label any multi-compound protocols as speculative pending clinical validation.
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/best-research-grade-hair-follicle-and-tissue-compounds-finasteride-vs-ghk-cu-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-17 13:04:072026-09-17 13:04:07Best Research-Grade Hair Follicle and Tissue Compounds: Finasteride vs. GHK-Cu and Copper Peptide Formulations
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top