Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: ghrh analogues

CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation

CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation

September 25, 2026/0 Comments/in Uncategorized/by

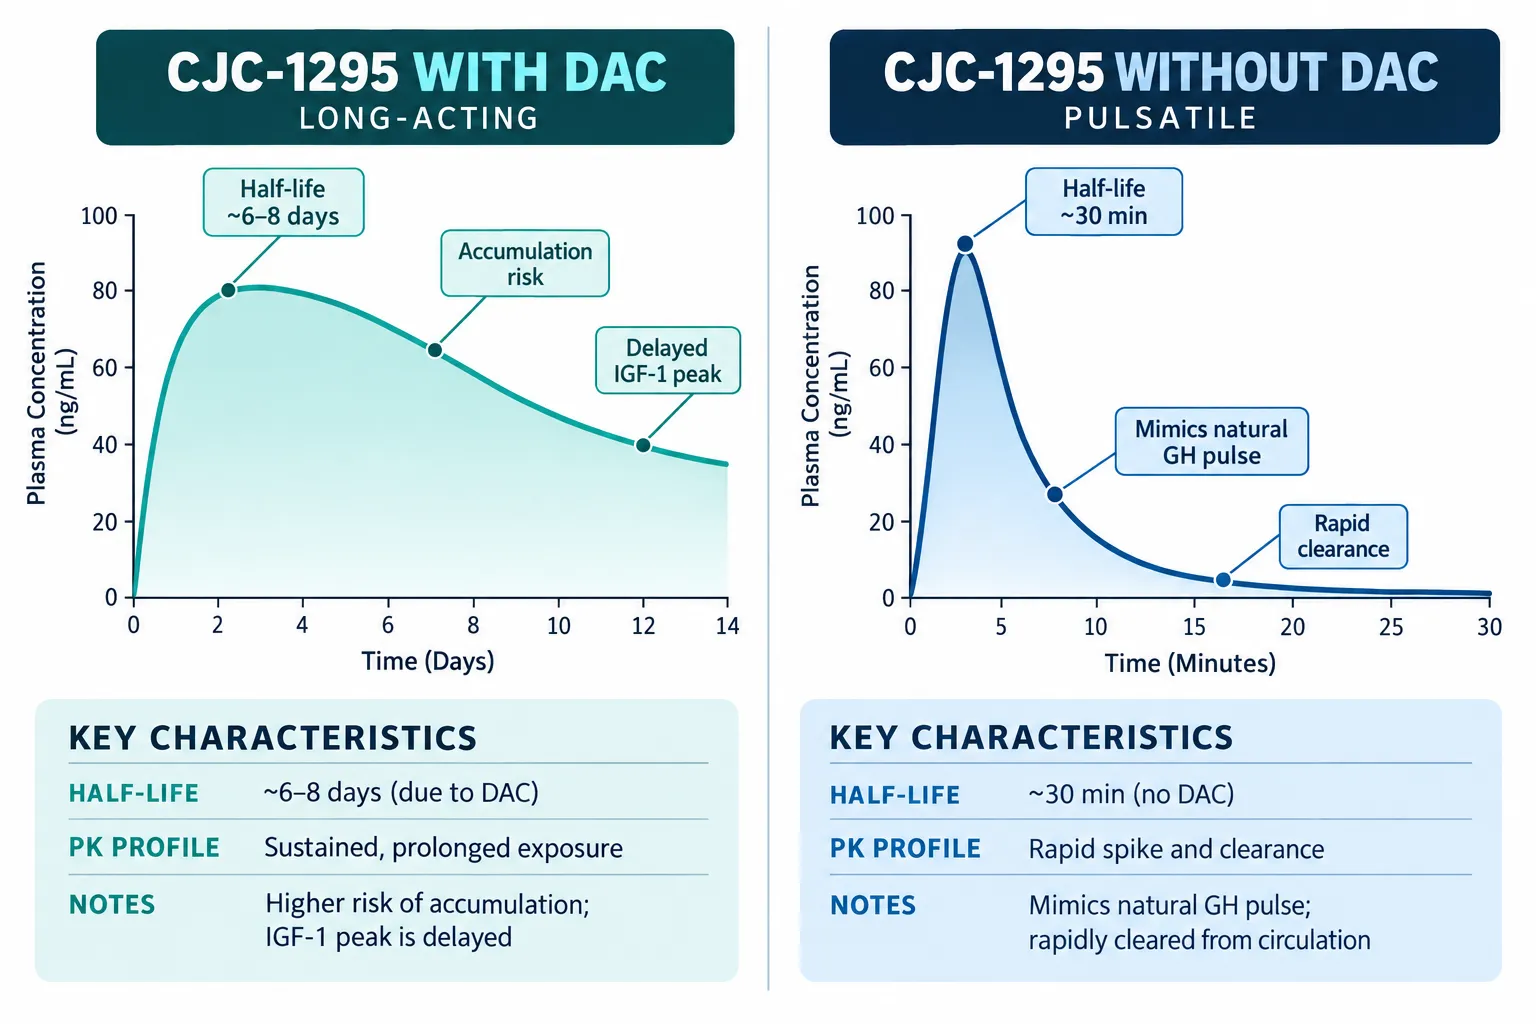
A single amino acid modification, the Drug Affinity Complex (DAC), extends CJC-1295's plasma half-life from roughly 30 minutes to approximately six to eight days. That difference is not merely pharmacokinetic trivia. It reshapes every decision a researcher makes: when to draw blood, how long to wait before the next treatment cycle, and whether an observed IGF-1 signal belongs to the compound or to residual accumulation from a prior dose. Understanding CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation is therefore foundational to producing reproducible, attributable preclinical data.

Key Takeaways

  • CJC-1295 without DAC has a half-life near 30 minutes, making it ideal for studying acute, pulsatile GH release; CJC-1295 with DAC sustains elevated GH and IGF-1 for days to weeks.
  • Sampling windows must be matched to the compound's kinetic profile, mismatched timing leads to missed peaks or inflated baseline readings.
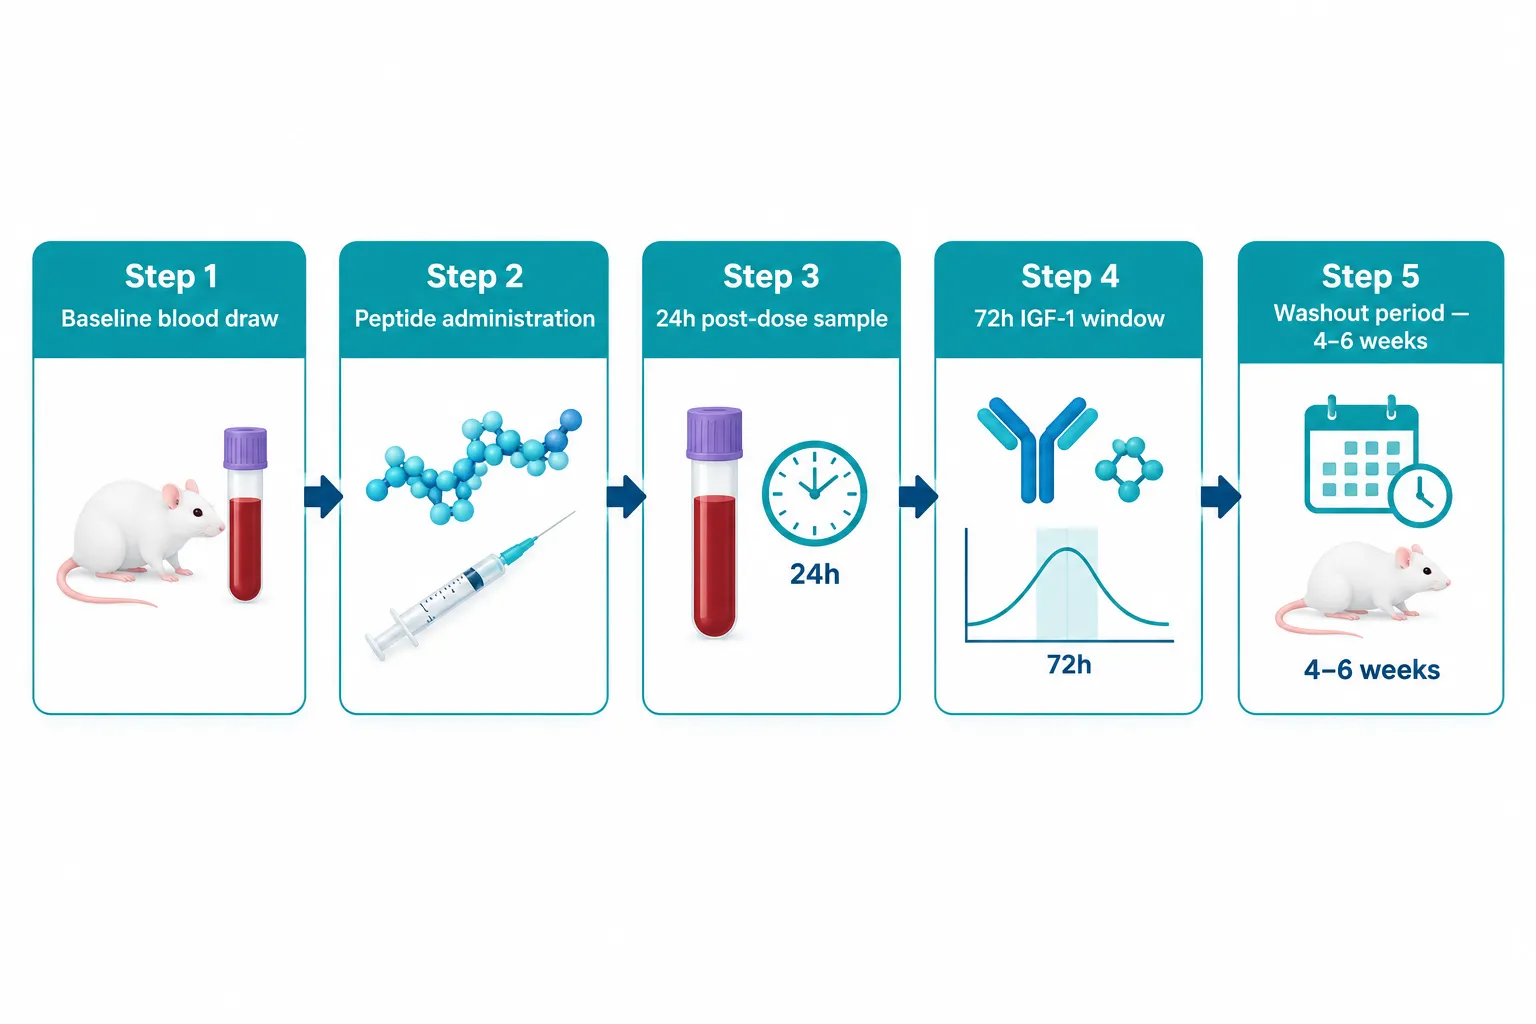
  • Washout for DAC-containing protocols requires a minimum of four to six weeks in rodent models to avoid carryover confounding.
  • IGF-1 attribution is the central interpretive challenge: sustained DAC exposure elevates tonic IGF-1, while the non-DAC form produces transient pulses that are easy to miss without frequent sampling.
  • Study design choices, dose interval, sample frequency, and washout length, differ substantially between the two forms and must be pre-specified in the protocol.

Half-Life Determines Everything Downstream
Half-Life Determines Everything Downstream

The pharmacokinetic contrast between the two forms is the logical starting point because every downstream design decision flows from it. CJC-1295 without DAC is a modified GHRH analogue that resists enzymatic cleavage long enough to reach pituitary receptors but is cleared within one to two hours in most rodent models. Its action is therefore discrete and pulse-like, closely mirroring endogenous GHRH activity.

CJC-1295 with DAC covalently binds to circulating albumin through its maleimido-propionyl group. This albumin linkage creates a depot effect, releasing active peptide slowly over days. In rat models, a single subcutaneous dose produces measurable GH elevation for up to five days and elevated IGF-1 for seven to ten days. The practical consequence is that a researcher who draws a single blood sample at 24 hours post-dose will capture very different biological states depending on which form was used.

For researchers exploring multi-peptide combinations, the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend illustrates how stacking long- and short-acting GHRH analogues complicates attribution further, reinforcing the need for precise kinetic mapping before interpreting outcomes.


Sampling Windows in Cell and Animal Studies: Matching Timing to Kinetics

Getting sampling windows right is where most preclinical CJC-1295 studies succeed or fail. The two forms demand fundamentally different schedules.

Without DAC: High-Frequency, Narrow Windows

Because the non-DAC form acts within minutes and clears rapidly, meaningful GH sampling must occur within 15 to 45 minutes post-administration in rodent models. A single time-point study will almost always underestimate peak GH. Recommended practice calls for serial sampling at 15, 30, 60, and 120 minutes to capture the full pulse shape. IGF-1, which responds more slowly to GH stimulation, should be sampled at 4, 8, and 24 hours to capture the downstream hepatic response.

Cell culture studies using the non-DAC form face an analogous challenge: peptide degradation in serum-containing media can reduce effective concentration within hours, so dosing intervals and media refresh schedules must be tightly controlled.

With DAC: Extended Windows, Accumulation Awareness

For the DAC form, single time-point sampling at 24 or 48 hours post-dose is more defensible, but researchers must account for accumulation across repeated doses. In a weekly dosing protocol over four weeks, plasma concentrations do not reach steady state until approximately the third dose. This means IGF-1 readings taken during weeks one and two reflect rising exposure, not steady-state biology. Comparing week-one IGF-1 to week-four IGF-1 without acknowledging this trajectory is a common interpretive error.

Recommended sampling in repeated-dose rodent studies with the DAC form:

  • Trough samples immediately before each dose (to track accumulation)
  • Peak samples 24 to 48 hours after each dose
  • IGF-1 at 72 hours post-dose, where the signal is most stable
  • A terminal bleed at least seven days after the final dose to distinguish residual compound from true washout baseline

For those working with related combination protocols, the Sermorelin, Ipamorelin, and CJC-1295 blend offers context on how multiple secretagogues interact when sampling schedules must account for overlapping kinetic profiles.


Washout Design and IGF-1 Interpretation
Washout Design and IGF-1 Interpretation

Washout is arguably the most underspecified element in published CJC-1295 animal studies. A compound with a six-to-eight-day half-life requires approximately five half-lives, roughly 30 to 40 days, to fall below 5% of peak plasma concentration. In practice, most expert guidance as of 2026 recommends a minimum four-to-six-week washout in rodent models before a crossover arm or a new treatment cycle begins.

Shorter washouts produce carryover elevation of IGF-1 that can be misattributed to a new intervention. This is particularly problematic in crossover designs where the DAC form is tested first.

Attributing GH Pulsatility vs. Sustained Elevation

The interpretive challenge is not just about timing, it is about biology. The non-DAC form preserves the pulsatile nature of GH secretion. Studies examining GH-dependent cellular processes such as lipolysis, protein synthesis, or IGF-1 receptor upregulation benefit from this pulsatility because it more closely models physiological signaling. The DAC form, by contrast, creates a tonic elevation that may saturate GH receptors and alter downstream sensitivity over time.

"Sustained GH elevation and pulsatile GH elevation are not interchangeable experimental conditions, they activate overlapping but distinct receptor dynamics."

Researchers must therefore specify in their protocols whether the biological question requires pulsatile or sustained GH exposure, and select the appropriate form accordingly. Mixing the two forms within a single study without a full washout between them produces data that cannot be cleanly attributed to either kinetic profile.

For additional context on how CJC-1295 is used alongside complementary peptides in research settings, the Tesamorelin, AOD9604, CJC-1295, and Ipamorelin 12mg blend page provides relevant formulation background. Similarly, researchers comparing secretagogue safety profiles may find the discussion on combining Tesamorelin with CJC Ipamorelin useful for contextualizing multi-compound study designs.


Practical Protocol Recommendations

Practical Protocol Recommendations

The following framework consolidates current best-practice guidance for preclinical researchers as of 2026:

Parameter Without DAC With DAC
GH sampling window 15-60 min post-dose 24-48 h post-dose
IGF-1 sampling window 4-24 h post-dose 48-72 h post-dose
Steady-state onset Single dose ~3rd dose (weekly protocol)
Minimum washout 48-72 hours 4-6 weeks
Crossover design risk Low High without full washout

For dose-ranging studies, the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend dosage guide and the corresponding dose reference offer practical starting points when CJC-1295 is part of a multi-peptide protocol.

Key protocol checkpoints:

  • Pre-specify whether the study question requires pulsatile or tonic GH exposure
  • Document accumulation phase separately from steady-state phase in multi-dose designs
  • Include a satellite group for washout verification if the study uses a crossover design
  • In cell studies, refresh media at intervals matched to the peptide's degradation rate in the specific media formulation used

Conclusion

The choice between CJC-1295 with DAC and without DAC is not simply a matter of dosing convenience, it is a fundamental experimental variable that determines when to sample, how long to wait, and how to interpret every GH or IGF-1 data point the study generates. Researchers who treat the two forms as interchangeable risk producing results that are either uninterpretable or actively misleading.

Actionable next steps for preclinical researchers:

  1. Define the biological question first, pulsatile or sustained GH exposure, then select the compound form that matches it.
  2. Build sampling schedules around the compound's actual kinetic profile, not convenience time-points.
  3. Enforce a minimum four-to-six-week washout for any DAC-containing protocol before a crossover or repeat cycle.
  4. Track trough concentrations across a multi-dose DAC study to confirm when steady state is reached before drawing mechanistic conclusions.
  5. Report the form used, the sampling schedule, and the washout length explicitly in methods sections so findings can be accurately compared across studies.

Rigorous attention to these design elements is what separates publishable, reproducible CJC-1295 research from data that raises more questions than it answers.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cjc-1295-with-dac-vs-without-dac-in-cell-and-animal-studies-sampling-windows-was.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-25 13:03:292026-09-25 13:03:29CJC-1295 With DAC vs. Without DAC in Cell and Animal Studies: Sampling Windows, Washout, and Interpretation
Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides

Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides

September 1, 2026/0 Comments/in Uncategorized/by

Men with obesity-related secondary hypogonadism can show testosterone levels up to 30% lower than age-matched lean controls, yet the endocrine axis disruption extends far beyond a single hormone. Understanding estrogen receptors, enclomiphene, and peptide hormones: how serms interface with GLP-class and growth hormone peptides is now central to advanced endocrine research protocols that model multiple hormonal axes simultaneously. As GLP-1 receptor agonists and GHRH analogues become fixtures in metabolic and body-composition research, the question of how a selective estrogen receptor modulator like enclomiphene fits into those multi-peptide frameworks has become increasingly important.

Key Takeaways

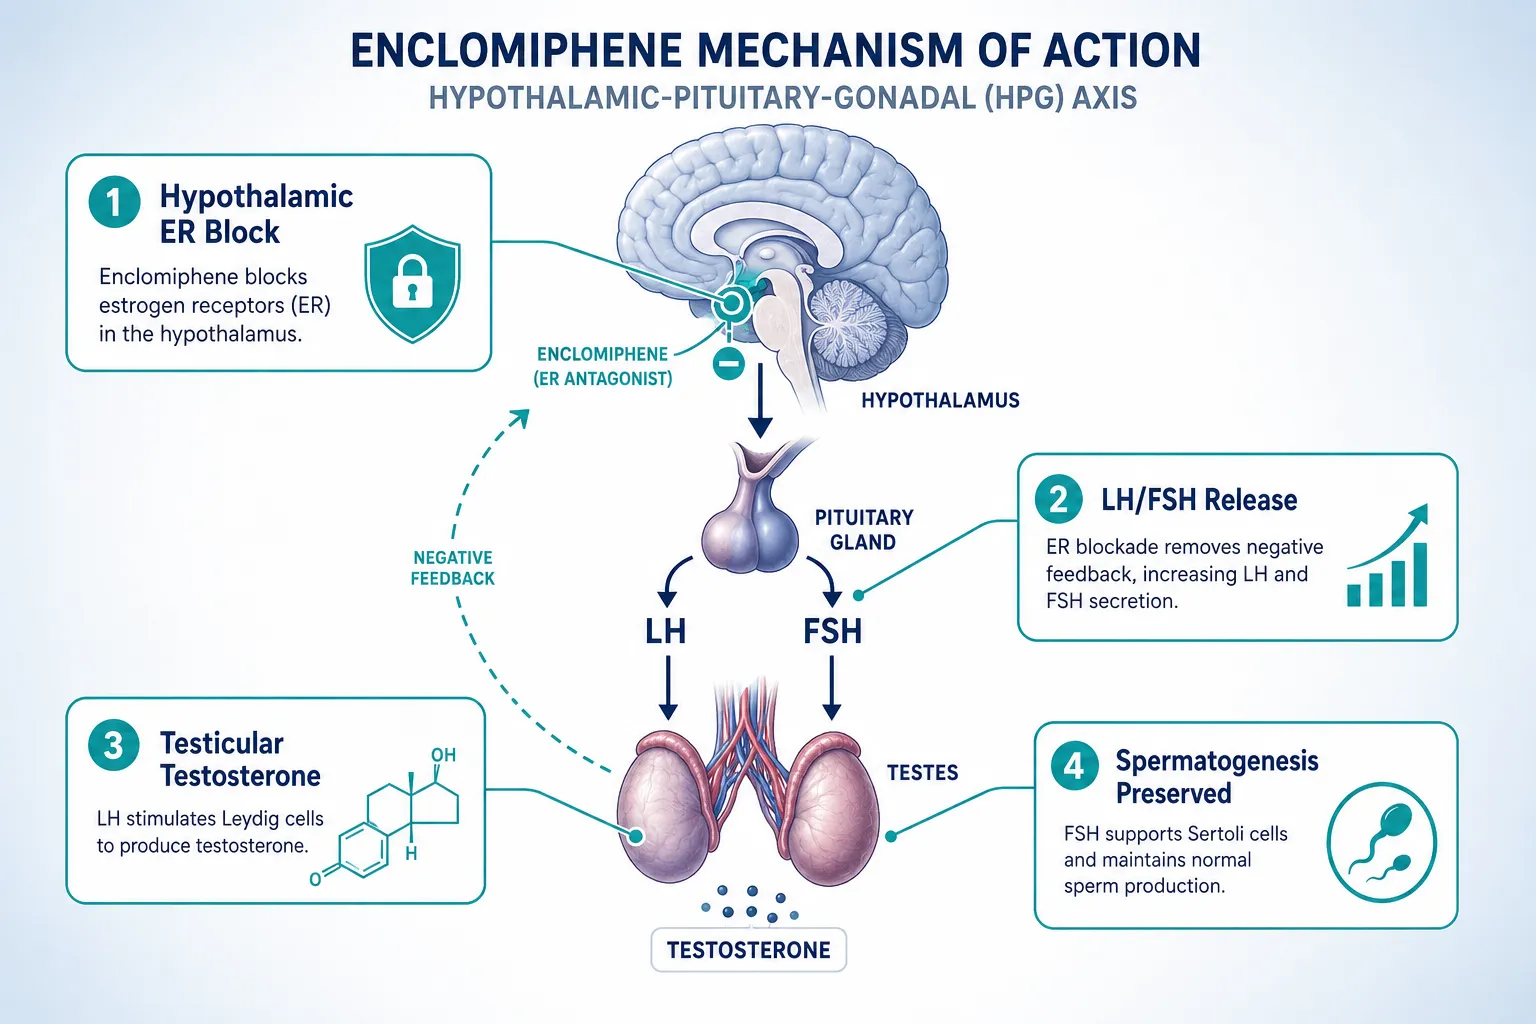
  • Enclomiphene blocks hypothalamic estrogen receptors to raise LH, FSH, and endogenous testosterone without suppressing spermatogenesis.
  • Systematic evidence shows serms can increase total testosterone by a mean of roughly 274 ng/dL versus placebo in functional hypogonadism.
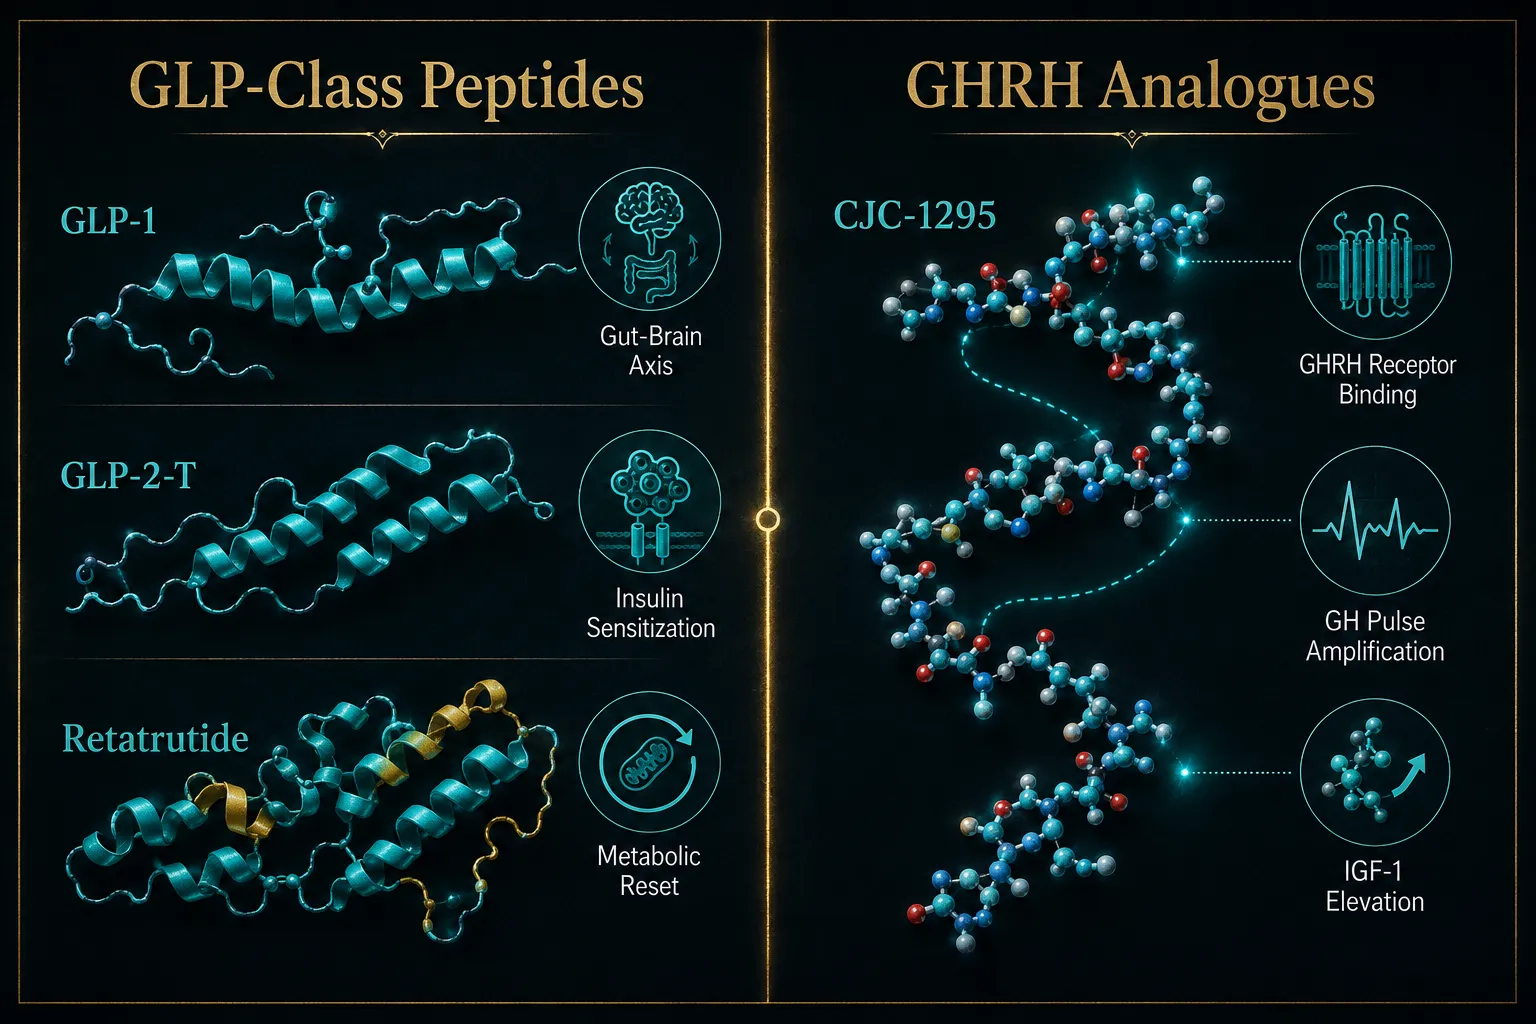
  • GLP-class peptides such as Retatrutide and GLP-2-T act on gut-brain and metabolic axes that indirectly influence sex hormone binding and HPG axis tone.
  • GHRH analogues like CJC-1295 amplify growth hormone pulses and raise IGF-1, creating a separate but intersecting endocrine signal relevant to serm protocols.
  • Formal combination trials of enclomiphene with GLP-class or GHRH peptides remain an open research frontier as of 2026.

How Enclomiphene Modulates Estrogen Receptors in the HPG Axis

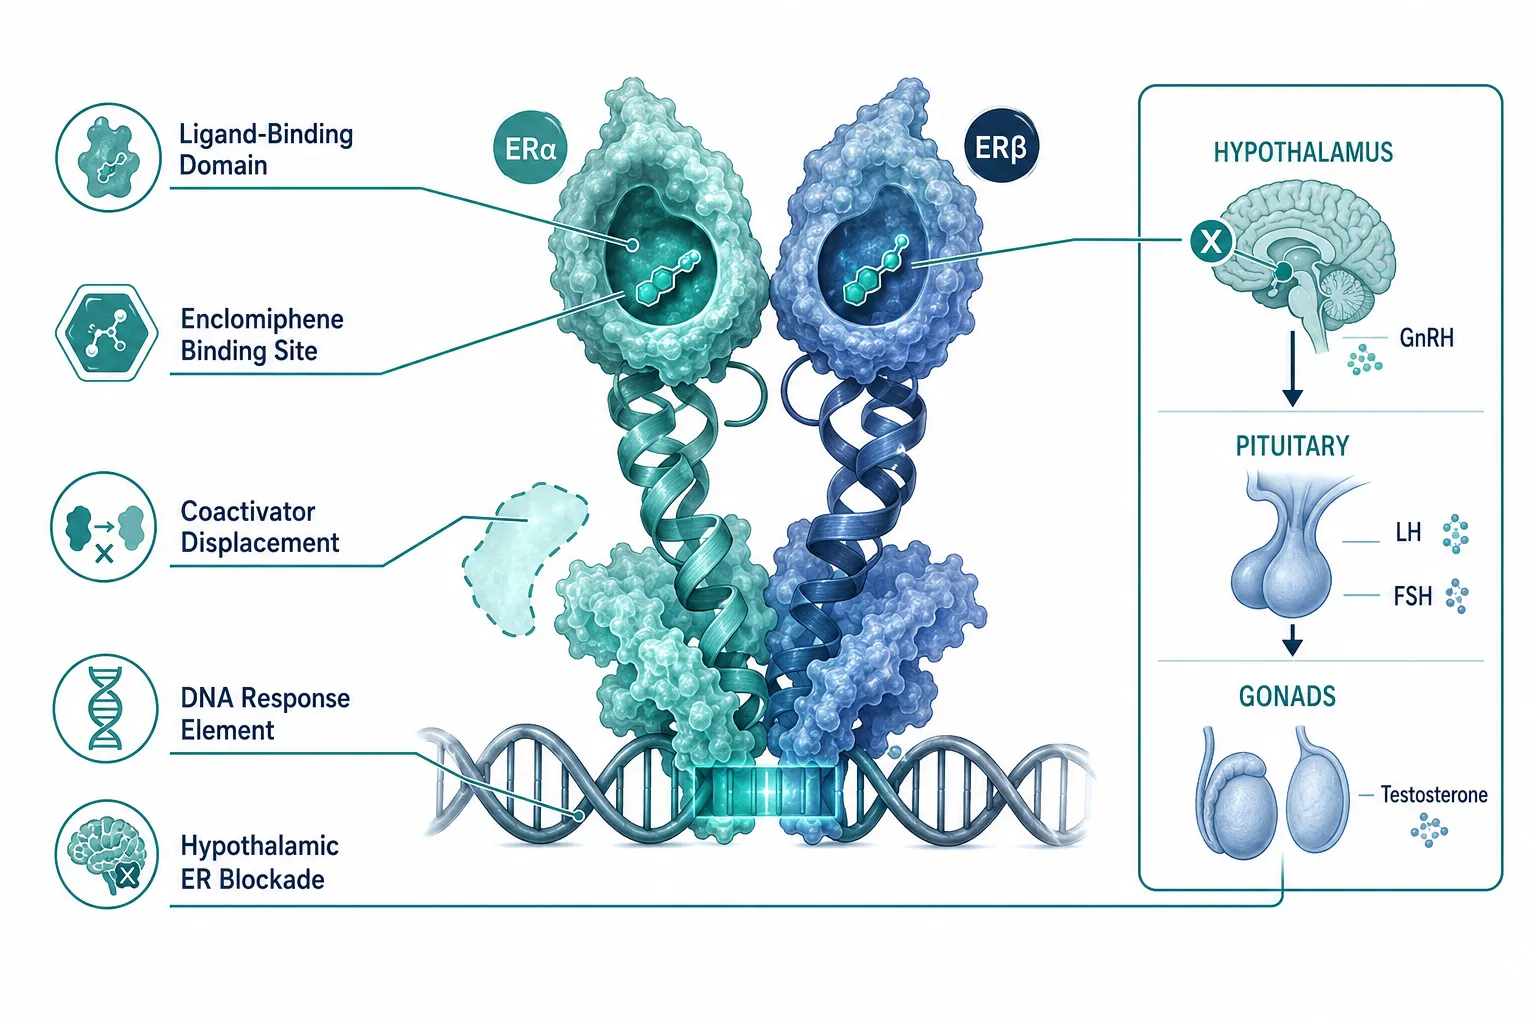
Enclomiphene is the trans-isomer of clomiphene. Unlike its cis-isomer zuclomiphene, it acts as a clean antagonist at hypothalamic estrogen receptors, blocking the negative feedback signal that estrogen normally sends to suppress gonadotropin-releasing hormone. The result is a coordinated rise in luteinizing hormone (LH) and follicle-stimulating hormone (FSH), which in turn drives endogenous testicular testosterone production.

How Enclomiphene Modulates Estrogen Receptors in the HPG Axis

This mechanism distinguishes enclomiphene sharply from exogenous testosterone replacement. Testosterone replacement shuts down the HPG axis through negative feedback; enclomiphene does the opposite. A systematic review and meta-analysis of ten randomized controlled trials covering 819 men found that serm therapy, primarily clomiphene and enclomiphene, raised total testosterone by a mean of approximately 274 ng/dL compared with placebo, while sperm parameters remained intact.

A 2026 British Society for Sexual Medicine position statement reinforces this picture. In one referenced RCT of 44 men, daily enclomiphene was non-inferior to transdermal testosterone at both 24 hours and 6 weeks. A retrospective series of 66 men showed a median testosterone increase of 5.76 nmol/L after roughly 9 months of therapy. For researchers exploring serm therapy protocols, these figures establish a meaningful hormonal baseline.

Why metabolic context matters: Men with obesity, type 2 diabetes, or metabolic syndrome often present with reversible hypothalamic-pituitary dysfunction, a profile where enclomiphene's upstream mechanism is particularly well-matched. Elevated aromatase activity in adipose tissue converts more testosterone to estradiol, deepening the hypothalamic feedback suppression that enclomiphene is designed to interrupt.

"Enclomiphene's value lies not just in raising testosterone, but in preserving the entire upstream signaling architecture, a distinction that matters enormously when modeling multi-axis endocrine protocols."

GLP-Class Peptides and Their Indirect Influence on Estrogen Receptor Signaling

The GLP-class of peptides, including GLP-1 receptor agonists, the dual/triple agonist Retatrutide (GLP-1/GIP/glucagon), and GLP-2-T analogues, operate primarily on gut-brain signaling, insulin secretion, and energy homeostasis. Their connection to estrogen receptor biology is indirect but mechanistically significant.

GLP-Class Peptides and Their Indirect Influence on Estrogen Receptor Signaling

GLP-1 receptor agonists reduce adipose mass. Because adipose tissue is the primary peripheral site of aromatase-driven estrogen synthesis in men, a meaningful reduction in fat mass lowers circulating estradiol. Lower estradiol reduces the hypothalamic estrogen receptor load that enclomiphene must overcome. In practical terms, a subject on a GLP-class agent may show a more responsive HPG axis to serm intervention.

Retatrutide, as a triple agonist targeting GLP-1, GIP, and glucagon receptors, produces more pronounced body-composition shifts than single-agonist agents. Research on tirzepatide peptide, a dual GLP-1/GIP agonist with a related mechanism, illustrates how GLP-class compounds can reshape the metabolic environment in which hormonal axes operate.

GLP-2-T analogues primarily target intestinal epithelial GLP-2 receptors, influencing gut integrity and nutrient absorption. Their relevance to estrogen receptor cross-talk is more distal but may include effects on enterohepatic estrogen recirculation, a pathway that modulates systemic estradiol levels and, consequently, hypothalamic feedback tone.

Researchers working with single peptide protocols often note that isolating one axis at a time provides cleaner data before combining agents, a principle that applies directly to serm-plus-GLP-class study design.

GHRH Analogues, Growth Hormone Peptides, and serm Protocol Integration

CJC-1295 is a synthetic GHRH analogue that extends the half-life of endogenous GHRH, amplifying pulsatile growth hormone release from the anterior pituitary and raising downstream IGF-1 levels. This creates a third endocrine axis, the GH/IGF-1 axis, that intersects with both the HPG axis and the metabolic effects of GLP-class peptides.

GHRH Analogues, Growth Hormone Peptides, and serm Protocol Integration

The relevance to estrogen receptor biology is bidirectional. IGF-1 has been shown to modulate estrogen receptor expression in multiple tissue types. Elevated GH and IGF-1 also influence body composition, reducing fat mass and increasing lean tissue, which feeds back into aromatase activity and circulating estradiol, the same variable that enclomiphene targets at the receptor level.

For researchers modeling endocrine axes, the interaction matrix looks like this:

Agent Primary Target Indirect Effect on ER Signaling
Enclomiphene Hypothalamic ER Direct blockade, raises LH/FSH
GLP-1/Retatrutide GLP-1/GIP/Glucagon R Reduces adipose aromatase substrate
CJC-1295 GHRH receptor IGF-1 modulates ER expression; body comp shift
GLP-2-T Intestinal GLP-2 R Enterohepatic estrogen recirculation effects

Researchers exploring serms in combination with growth hormone peptides should account for these intersecting signals when designing outcome measures. Sports peptides research has long recognized that GH-axis and sex-hormone-axis interventions produce non-additive effects, a principle that extends to serm-plus-GHRH analogue modeling.

Enclomiphene's clinical profile also makes it suitable for populations where erythrocytosis risk from testosterone replacement is a concern, a relevant consideration when subjects are simultaneously on GH-stimulating peptides that affect red blood cell precursor signaling.

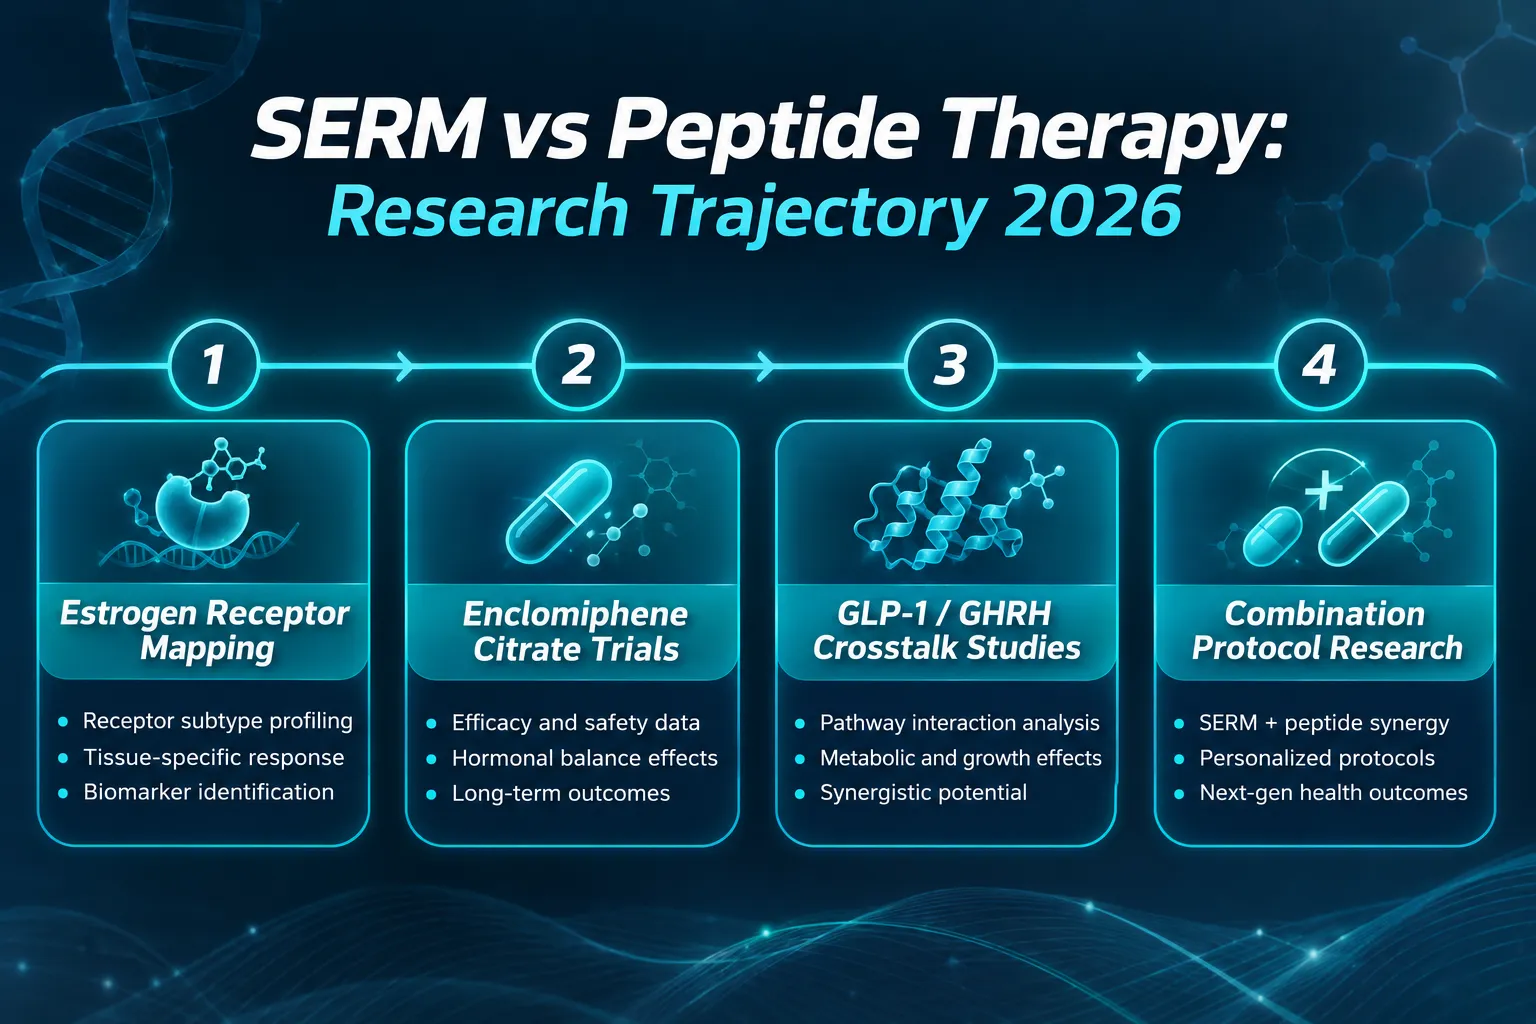
As of 2026, formal combination trials pairing enclomiphene with GLP-class agents or GHRH analogues have not been published. This represents a significant gap in the literature and a clear frontier for structured research protocols.

Conclusion

The intersection of estrogen receptors, enclomiphene, and peptide hormones, how serms interface with GLP-class and growth hormone peptides, is one of the most mechanistically rich areas in current endocrine research. Enclomiphene provides a targeted, fertility-preserving tool for HPG axis restoration. GLP-class peptides reshape the metabolic environment that determines how much estrogenic feedback the hypothalamus receives. GHRH analogues like CJC-1295 add a third dimension through IGF-1-mediated effects on receptor expression and body composition.

Actionable next steps for researchers and clinicians:

  • Map baseline estradiol, LH, FSH, and testosterone before introducing any multi-agent protocol.
  • Consider GLP-class-driven fat-mass reduction as a preparatory phase that may enhance enclomiphene responsiveness.
  • Use validated assays for both total and free testosterone, IGF-1, and estradiol when modeling combined serm-plus-peptide protocols.
  • Monitor spermatogenesis parameters if fertility preservation is a stated research or clinical objective.
  • Prioritize single-axis baseline data before combining enclomiphene with GHRH analogues to isolate each variable's contribution.

The endocrine axes do not operate in isolation. Research protocols that treat them as interconnected systems, rather than independent targets, will generate the most meaningful data as this field matures.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/estrogen-receptors-enclomiphene-and-peptide-hormones-how-serms-interface-with-gl.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-01 13:05:082026-09-01 13:05:08Estrogen Receptors, Enclomiphene, and Peptide Hormones: How serms Interface With GLP-Class and Growth Hormone Peptides
Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides

Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides

August 28, 2026/0 Comments/in Uncategorized/by

Fewer than 15% of men diagnosed with functional hypogonadism in 2026 are offered non-testosterone pharmacological alternatives, yet enclomiphene citrate, a selective estrogen receptor modulator (serm), has quietly accumulated a substantial research record that intersects with some of the most active areas in peptide science. Understanding estrogen receptors and enclomiphene, and how serm research interfaces with polypeptide hormones and GLP-class peptides, is no longer a niche academic exercise. It is a practical framework for clinicians, researchers, and informed patients navigating a rapidly expanding hormonal-optimization landscape.

Key Takeaways

  • Enclomiphene blocks hypothalamic estrogen receptors to amplify GnRH, LH, and FSH output, preserving endogenous testosterone production.
  • Emerging evidence points to a bidirectional crosstalk between estrogen receptor signaling and GLP-1 class peptide pathways, particularly in the arcuate nucleus.
  • Polypeptide hormones such as GHRH analogues and GLP-class peptides operate through distinct receptor families but share downstream metabolic overlap with serm-driven hormonal cascades.
  • As of 2026, enclomiphene remains off-label for male hypogonadism in most jurisdictions, while GLP-1 receptor agonists hold broad regulatory approval.
  • Purity and third-party verification of research peptides are critical variables when studying these interactions at the lab level.

How Enclomiphene Targets Estrogen Receptors

Enclomiphene is the trans-isomer of clomiphene citrate. While clomiphene contains both the zuclomiphene (cis) and enclomiphene (trans) isomers, the trans form carries most of the receptor-antagonist activity at the hypothalamic level. It binds competitively to estrogen receptor alpha (ERa) and estrogen receptor beta (ERb) in the hypothalamus and pituitary, blocking the negative feedback that estradiol normally exerts on gonadotropin-releasing hormone (GnRH) pulsatility.

How Enclomiphene Targets Estrogen Receptors

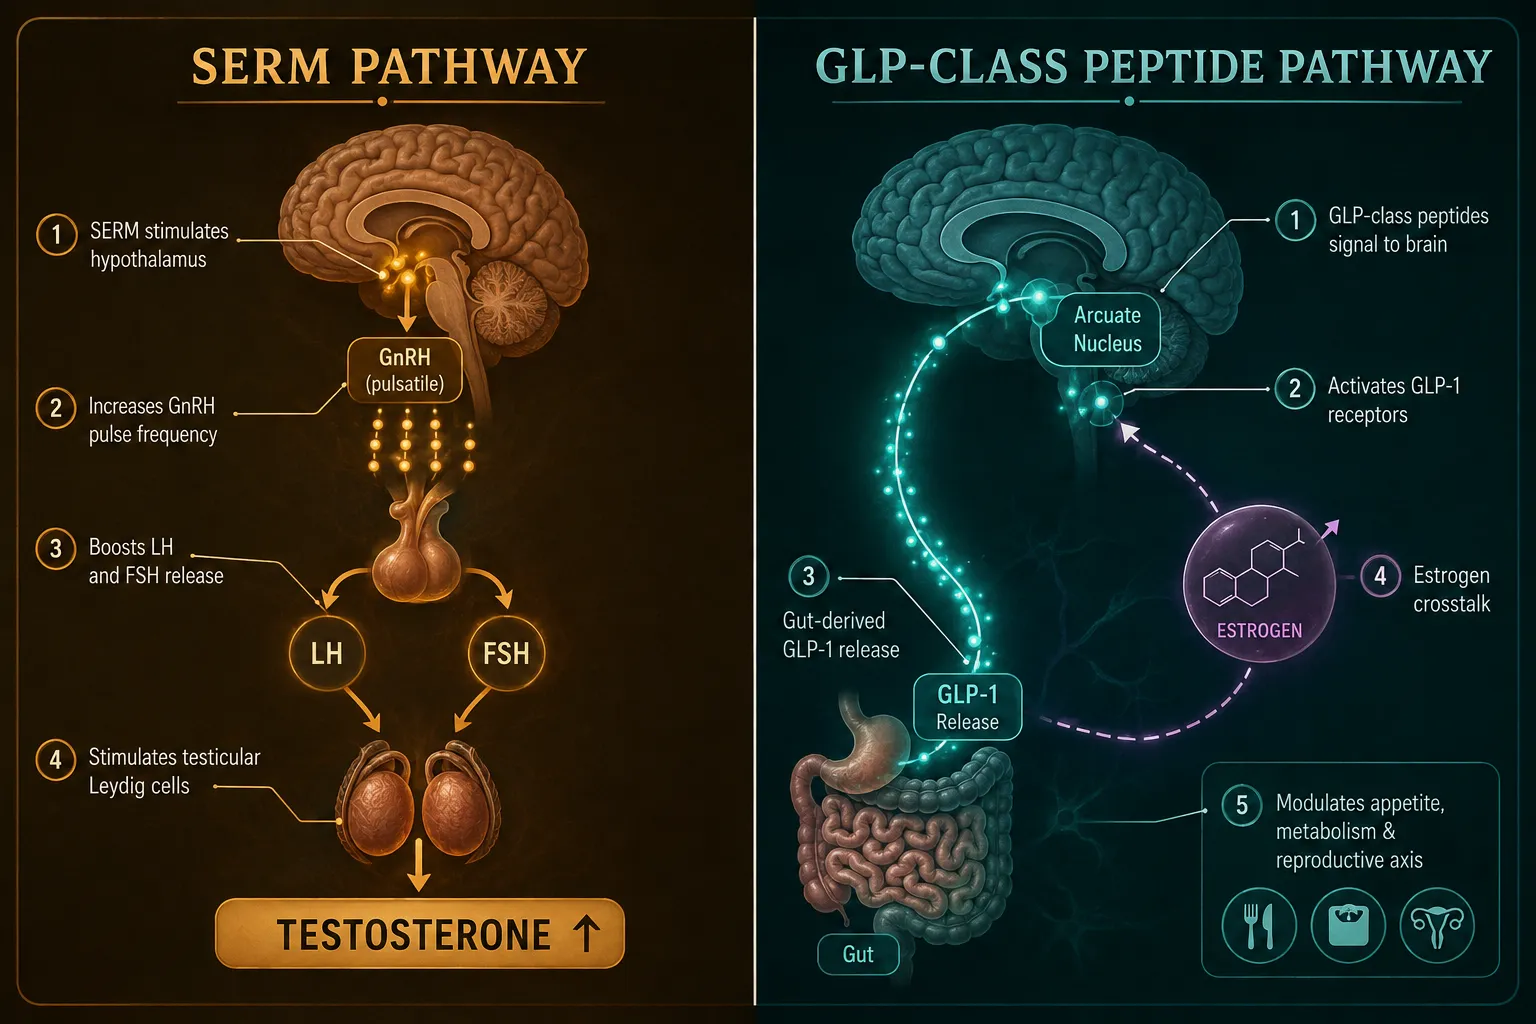
The result is a measurable increase in GnRH pulse frequency, which drives luteinizing hormone (LH) and follicle-stimulating hormone (FSH) secretion from the anterior pituitary. Elevated LH then stimulates Leydig cell testosterone synthesis in the testes. This mechanism is fundamentally different from exogenous testosterone replacement, which suppresses the hypothalamic-pituitary-gonadal (HPG) axis through negative feedback. Enclomiphene preserves, and actively stimulates, endogenous production.

Key receptor pharmacology points:

  • ERa blockade in the hypothalamus is the primary driver of GnRH disinhibition
  • ERb activity in peripheral tissues influences mood, bone density, and cardiovascular tone
  • Enclomiphene's selectivity profile differs from tamoxifen and raloxifene, making direct class comparisons imprecise

A 2025 systematic review comparing enclomiphene to testosterone replacement in male functional hypogonadism found that enclomiphene produced comparable testosterone normalization while maintaining sperm production, a clinically significant advantage for men of reproductive age.

serm Research Interfaces With Polypeptide Hormones: The HPG-Peptide Connection

The phrase "estrogen receptors and enclomiphene: how serm research interfaces with polypeptide hormones and GLP-class peptides" captures a genuinely complex biological intersection. The HPG axis does not operate in isolation. It is modulated by a network of polypeptide signals, including growth hormone-releasing hormone (GHRH), kisspeptin, and GLP-1 receptor agonists.

serm Research Interfaces With Polypeptide Hormones: The HPG-Peptide Connection

GHRH analogues and the serm context

GHRH analogues such as sermorelin and CJC-1295 stimulate growth hormone (GH) release from the anterior pituitary through GHRH receptor activation. Research into sermorelin and ipamorelin CJC-1295 combinations has shown that GH secretion interacts with sex hormone-binding globulin (SHBG) levels, indirectly influencing free testosterone availability. When enclomiphene raises total testosterone, the concurrent use of GHRH analogues may alter SHBG dynamics, creating a meaningful lab-level variable.

For researchers exploring IPA sermorelin stack protocols, understanding how estrogen receptor modulation affects the downstream hormonal environment is essential for interpreting assay results accurately.

GLP-1 class peptides: the emerging crosstalk

GLP-1 receptor agonists, originally developed for glycemic control, have revealed unexpected neuroendocrine activity. GLP-1 receptors are expressed in the arcuate nucleus of the hypothalamus, a region dense with kisspeptin neurons that directly regulate GnRH pulsatility. Estrogen receptors are co-expressed in the same neuronal populations.

"The arcuate nucleus functions as a convergence point where estrogen signaling, GLP-1 receptor activation, and kisspeptin-driven GnRH control interact in ways that current research is only beginning to map."

This means that a serm like enclomiphene, acting on hypothalamic ERa, may have functional crosstalk with GLP-1 receptor signaling in the same anatomical region. Researchers working with GLP-1 peptides in metabolic or neuroendocrine models should account for this overlap when designing experiments that also involve ER-modulating compounds.

The GLP-2 peptide class, while primarily intestinotrophic, also shows central nervous system expression patterns that warrant attention in multi-peptide research designs.

Research Trajectory and Practical Positioning in 2026

As of 2026, the regulatory landscape remains fragmented. Enclomiphene holds no major market authorization specifically for male hypogonadism in the United States or European Union, though off-label prescribing is common in men's health clinics. GLP-1 receptor agonists, by contrast, carry broad approvals for type 2 diabetes and obesity management, with ongoing trials in cardiovascular and neurodegenerative indications.

Research Trajectory and Practical Positioning in 2026

Positioning comparison at a glance:

Factor Enclomiphene (serm) GLP-1 Class Peptides
Primary target Hypothalamic ERa/ERb GLP-1 receptor (gut, brain)
Regulatory status (2026) Off-label (most jurisdictions) Approved (metabolic indications)
HPG axis effect Stimulatory (raises LH, FSH, T) Indirect (arcuate nucleus crosstalk)
Fertility preservation Yes Not established
Research peptide purity needs High High

For lab-level studies examining these interactions, sourcing lab tested peptides with verified purity documentation is non-negotiable. Contaminants or isomeric impurities can confound receptor-binding assays and produce misleading downstream hormone data.

Researchers interested in the growth hormone axis should also review tesa peptide benefits data, as tesa's effects on visceral fat and IGF-1 levels create additional metabolic variables relevant to any multi-compound hormonal study design.

Forward-looking analyst perspective (speculative): The most likely near-term research direction involves combination protocols that pair serm-driven HPG axis stimulation with GLP-1 receptor agonism to address both hypogonadism and metabolic syndrome simultaneously. This is not yet supported by randomized controlled trial data, but mechanistic rationale is strong enough to justify structured pilot studies.

Conclusion

Estrogen receptors and enclomiphene represent a well-characterized pharmacological axis. How serm research interfaces with polypeptide hormones and GLP-class peptides is a newer and more complex question, one that demands rigorous methodology, verified reagents, and a clear understanding of the convergent biology at the hypothalamic level.

Actionable next steps for researchers and clinicians:

  1. Map estrogen receptor expression alongside GLP-1 receptor distribution in any neuroendocrine study design that involves enclomiphene or related serms.
  2. Account for SHBG dynamics when combining GHRH analogues with serm protocols, as free hormone availability will shift.
  3. Use only third-party verified, lab tested peptides to eliminate purity as a confounding variable.
  4. Monitor the regulatory environment closely, enclomiphene's off-label status may shift as trial data accumulates through 2026 and beyond.
  5. Treat GLP-1 and serm crosstalk findings as hypothesis-generating until controlled trial data is available.

The intersection of serm pharmacology and peptide hormone research is not a fringe topic. It is where the next generation of hormonal optimization protocols will be built.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/estrogen-receptors-and-enclomiphene-how-serm-research-interfaces-with-polypeptid.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-28 13:05:392026-08-28 13:05:39Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top