

What Does MCHC Mean in Peptide Research? Interpreting Hemoglobin Indices When Evaluating GLP-Class and Tissue-Repair Models
Fewer than 15% of published preclinical peptide studies list MCHC as a primary endpoint, yet researchers routinely flag unexpected shifts in this index and struggle to interpret what they mean. Understanding what does MCHC mean in peptide research, and how to interpret hemoglobin indices when evaluating GLP-class and tissue-repair models, is a practical skill that separates rigorous data review from guesswork.
Key Takeaways
- MCHC (Mean Corpuscular Hemoglobin Concentration) measures hemoglobin density inside red blood cells and is calculated as hemoglobin divided by hematocrit, expressed in g/dL.
- In peptide research, MCHC functions as a secondary safety and physiology marker, not a primary efficacy endpoint.
- Low MCHC (hypochromia) most often signals iron deficiency, chronic inflammation, or sample dilution rather than a direct peptide effect.
- High MCHC (hyperchromia) in preclinical panels frequently reflects laboratory artifact, particularly hemolysis from poor sample handling.
- MCHC should always be interpreted alongside MCV, RDW, and full study context before attributing changes to any peptide compound.
Defining MCHC: Calculation, Normal Ranges, and the Erythrocyte Index Hierarchy
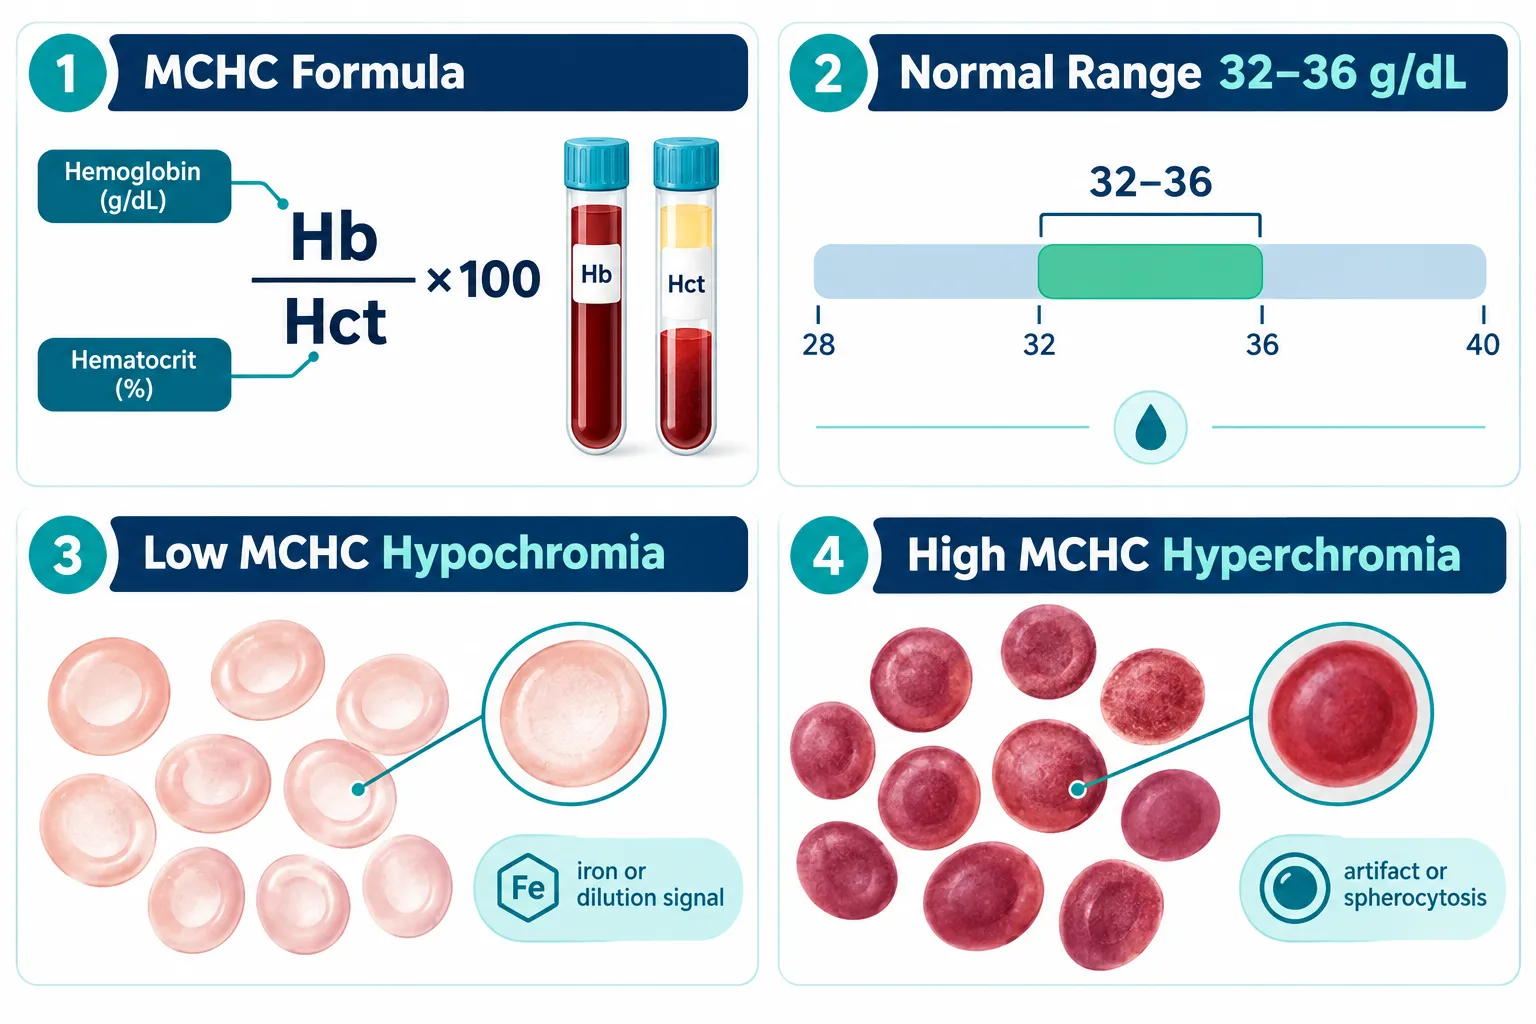
MCHC stands for Mean Corpuscular Hemoglobin Concentration. It quantifies how much hemoglobin is packed into a given volume of red blood cells. The formula is straightforward:
MCHC (g/dL) = (Hemoglobin / Hematocrit) x 100
In most mammalian species used in preclinical research, the reference range sits between 32 and 36 g/dL. Values below this threshold indicate hypochromia (pale, hemoglobin-poor cells). Values above suggest hyperchromia, though true biological hyperchromia is rare.
Within the broader erythrocyte index hierarchy, MCHC ranks below MCV (Mean Corpuscular Volume) and RDW (Red Cell Distribution Width) in diagnostic weight. Here is how the indices compare:
| Index | What It Measures | Research Priority |
|---|---|---|
| MCV | Average red cell size | High |
| RDW | Size variation across cells | High |
| MCH | Average hemoglobin per cell | Moderate |
| MCHC | Hemoglobin concentration per cell volume | Supportive |
MCHC is most useful when read as part of this full panel, not in isolation. Researchers sourcing compounds through platforms that emphasize building robust peptide benchmarks will recognize that baseline CBC panels, including MCHC, are part of responsible quality-control workflows.
Why MCHC Matters When Interpreting Hemoglobin Indices in GLP-Class Models
GLP-1 receptor agonist (GLP-RA) compounds have become central to metabolic research. When reviewing CBC safety data from GLP-class studies, MCHC appears as a secondary safety lab rather than a target biomarker. Its role is to confirm that metabolic changes driven by energy restriction, body composition shifts, or altered nutrient absorption are not producing clinically meaningful hematologic stress.
Researchers working with GLP-1 peptide sourcing and generational research concepts should note that caloric restriction models, common in GLP-RA efficacy studies, can mildly suppress MCHC through reduced dietary iron intake. This is a model-design artifact, not a compound toxicity signal.
Key considerations for GLP-class CBC interpretation:
- Weight loss velocity can transiently alter plasma volume, diluting hemoglobin concentration and lowering apparent MCHC.
- Visceral fat mobilization studies, such as those explored in visceral fat research models, may produce mild hemodilution as fluid compartments shift.
- GLP-2-class compounds, which target intestinal repair and nutrient absorption, carry a more direct theoretical link to iron and B12 uptake, making MCHC monitoring more relevant in those specific models.
For researchers evaluating next-generation triple-agonist compounds, resources on GLP-3 for sale and triple agonist research planning provide useful context on how expanded receptor profiles may affect systemic physiology, including hematologic readouts.

MCHC in Tissue-Repair Peptide Models: A Practical Interpretation Framework
Tissue-repair peptides, including TB-500 analogs and mitochondria-targeting compounds, introduce different considerations for hemoglobin index interpretation. Researchers following TB-500 controlled experimental models and QC workflow already understand that angiogenesis-promoting compounds can alter red cell dynamics through vascular remodeling rather than direct erythropoietic effects.
For mitochondria-targeted peptides, the relationship between cellular energy metabolism and red cell lifespan is an active area of interest. Work in SS-31 mitochondrial research and related SS-31 kidney health research highlights how oxidative stress reduction may indirectly support erythrocyte membrane integrity, a variable that influences MCHC readings over longer study durations.
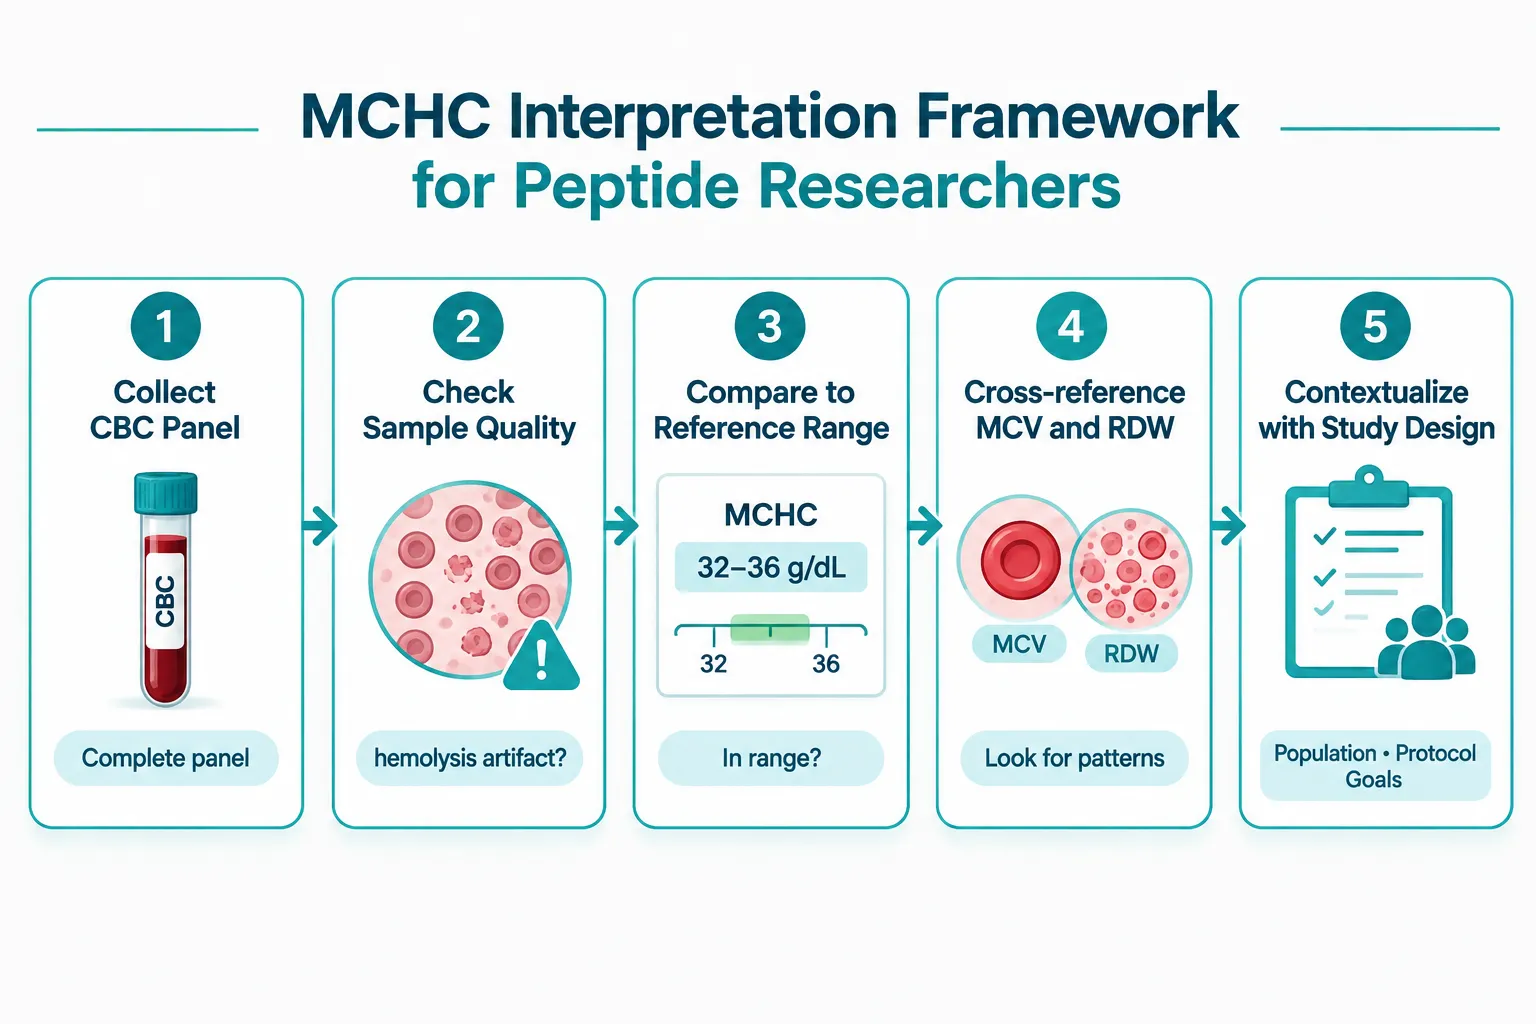
A practical five-step MCHC interpretation framework for peptide researchers:
- Verify sample quality first. Hemolysis from poor venipuncture or freeze-thaw cycling is the single most common cause of falsely elevated MCHC. Confirm sample integrity before drawing conclusions.
- Check the full CBC panel. An isolated MCHC shift without corresponding MCV or RDW changes is more likely an artifact than a biological signal.
- Compare against species-specific reference ranges. Murine, rat, and canine reference ranges differ meaningfully from human norms.
- Cross-reference study design variables. Diet, hydration status, and blood collection timing all affect MCHC independently of any peptide compound.
- Assign interpretive weight proportionally. MCHC is a supporting character in the CBC story, not the lead.
As of late 2026, the published literature contains very few peptide-specific MCHC studies. Most available data comes from broader hematology safety panels embedded in metabolic or regenerative medicine trials. This gap means researchers must apply general hematology principles carefully rather than relying on peptide-specific MCHC benchmarks.
Conclusion
Understanding what does MCHC mean in peptide research, and how to interpret hemoglobin indices when evaluating GLP-class and tissue-repair models, ultimately comes down to context. MCHC is a reliable supporting marker when used correctly, but it is frequently misread when treated as a standalone signal.
Actionable next steps for peptide researchers in 2026:
- Always collect a full CBC panel, not individual indices, as part of baseline and endpoint safety monitoring.
- Document sample collection conditions meticulously to rule out hemolysis artifacts before flagging MCHC shifts.
- When MCHC deviates from reference range, cross-check MCV, RDW, and reticulocyte count before attributing the change to a peptide compound.
- For GLP-class models, account for caloric restriction and fluid redistribution as confounding variables in hematologic data.
- For tissue-repair and mitochondria-targeting models, monitor MCHC trends over time rather than at single time points to distinguish transient from sustained changes.
Rigorous interpretation of hemoglobin indices strengthens the overall quality of peptide research data and supports more reliable conclusions across all model types.