Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: igf-1 research

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show

September 2, 2026/0 Comments/in Uncategorized/by

Growth hormone secretagogue research has quietly shifted gears. Where earlier studies focused almost exclusively on peak GH output, the conversation around CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show has expanded to include tissue recovery timelines, glucose-handling endpoints, and combination stacking strategies that were barely discussed five years ago. Researchers and clinicians in 2026 are asking more nuanced questions, not just "does IGF-1 rise?" but "what does that rise actually do in a metabolic or recovery context?"

Key Takeaways

  • CJC‑1295 with DAC offers a prolonged half-life suited to weekly dosing, while the no-DAC form aligns better with circadian-timed, daily micro-dose protocols.
  • Stacking CJC‑1295 with ipamorelin has become the dominant 2026 protocol pattern in both clinical and research settings.
  • IGF-1 elevation is well-documented, but hard endpoints for recovery and body composition remain limited in the published evidence base.
  • Desensitization risk with the DAC form makes structured washout periods a standard protocol feature in 2026 monographs.
  • Combination protocols now extend to Tesamorelin and metabolic peptides, broadening the research scope beyond classic GH modeling.

Understanding the Two Forms: DAC vs. No-DAC
Understanding the Two Forms: DAC vs. No-DAC

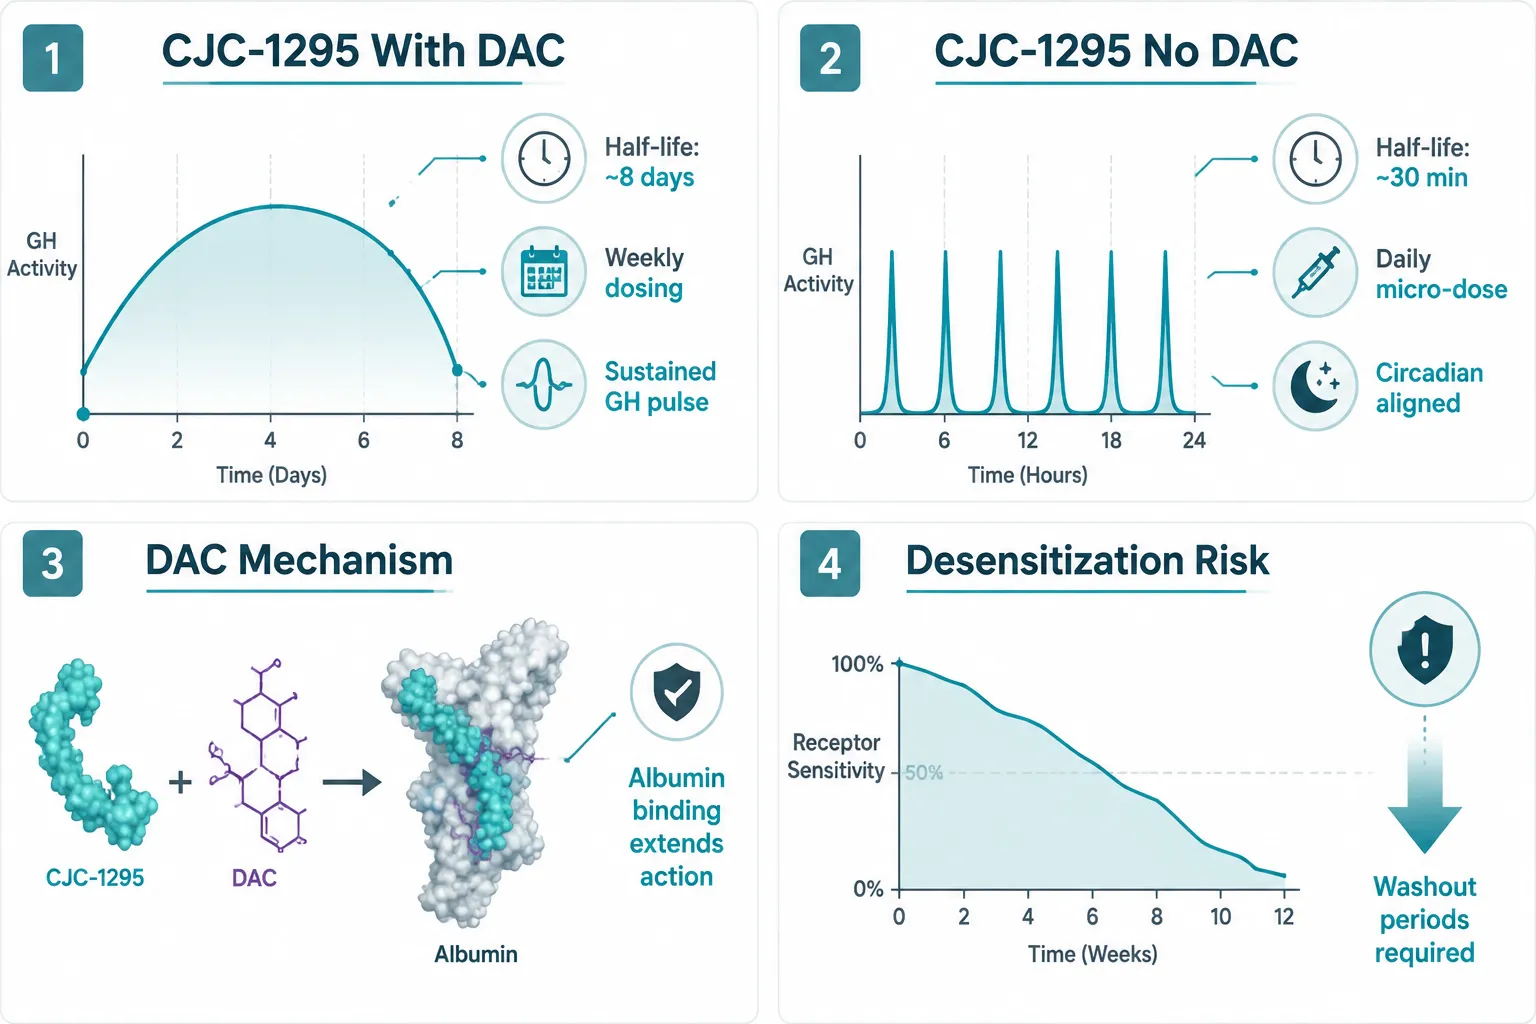
The core structural difference between the two variants drives nearly every protocol decision. CJC‑1295 with DAC (Drug Affinity Complex) binds to albumin in the bloodstream, dramatically extending its half-life to approximately eight days. This makes once-weekly or twice-monthly dosing pharmacologically feasible and reduces injection burden in longer research cycles.

CJC‑1295 without DAC, sometimes called Modified GRF(1-29), has a half-life of roughly 30 minutes. That short window is not a disadvantage in every context. Researchers exploring circadian-aligned dosing argue that brief, timed pulses more closely mimic the body's natural growth hormone release patterns, particularly when administered before sleep or around training windows.

Key pharmacokinetic comparison:

Feature With DAC Without DAC
Half-life ~8 days ~30 minutes
Dosing frequency Weekly or bi-weekly Daily or twice daily
GH pulse pattern Sustained elevation Acute, pulsatile
Desensitization risk Higher Lower
Protocol washout need Yes, structured Minimal

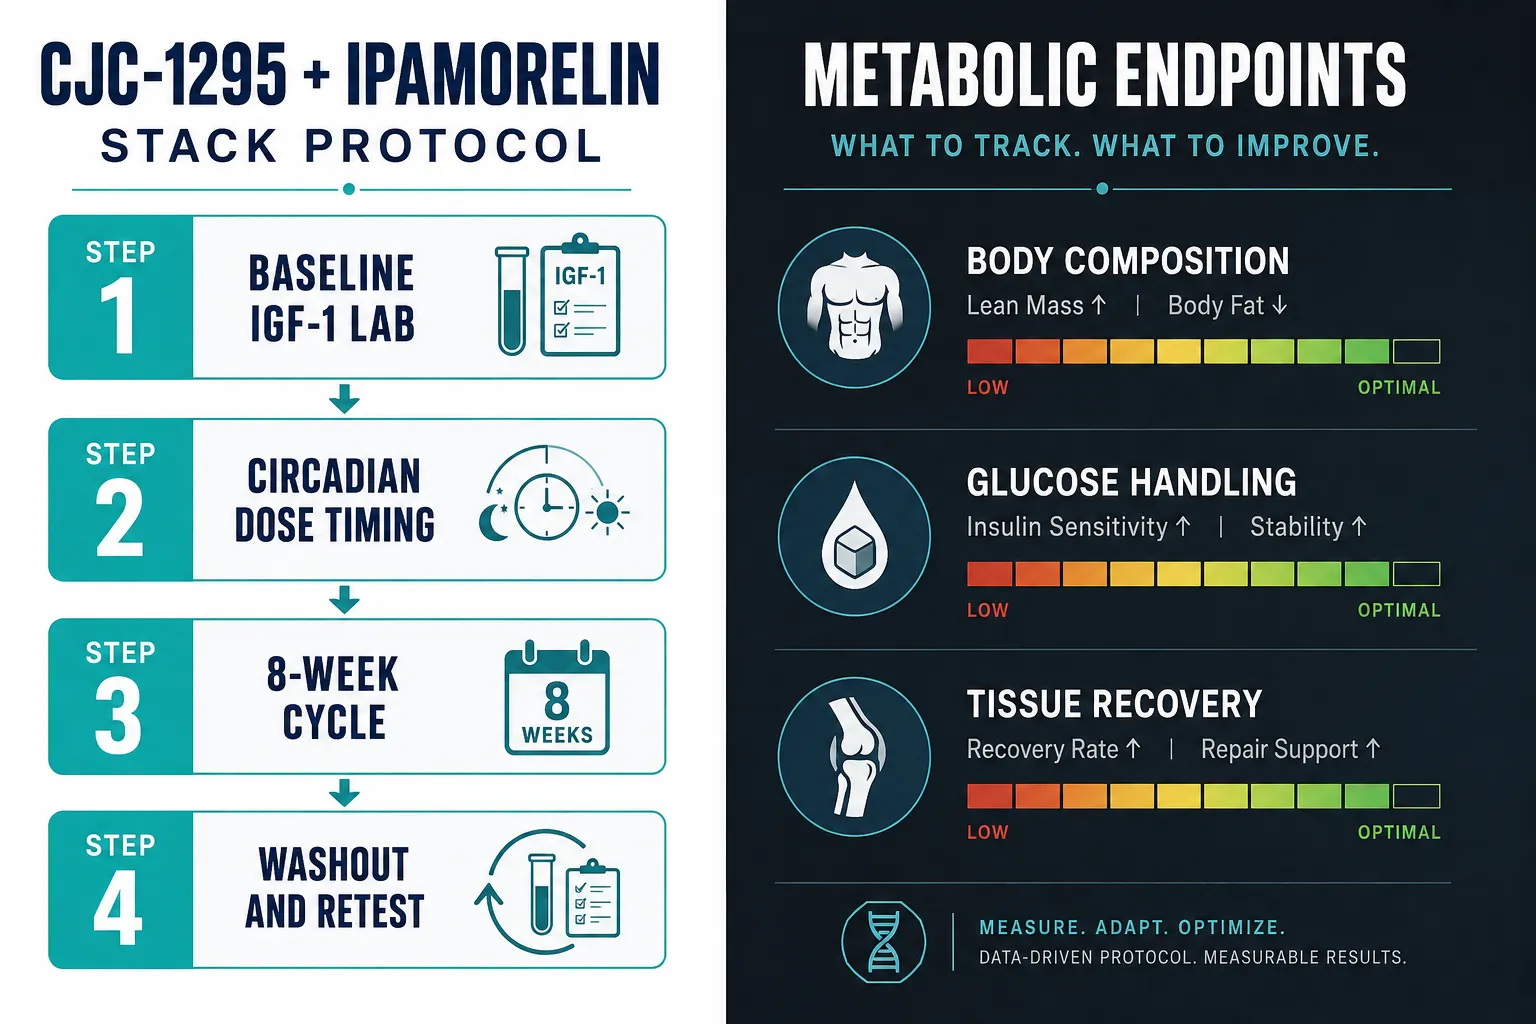
Desensitization is a genuine concern with the DAC form. Prolonged receptor stimulation can blunt pituitary responsiveness over time. Current somatotropin research protocols in 2026 address this by building in four-to-six-week washout periods after eight-to-twelve-week active cycles.

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show About Combination Stacking
CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show About Com

The most significant protocol shift in 2026 is the near-universal pairing of CJC‑1295 with ipamorelin. Ipamorelin is a selective ghrelin receptor agonist that stimulates GH release through a complementary pathway. Together, the two peptides produce a synergistic GH pulse without the cortisol or prolactin elevation associated with older secretagogues.

"The combination of a GHRH analog with a selective ghrelin mimetic has become the reference stack in 2026 protocol literature, it amplifies the GH signal while keeping the hormonal side-effect profile narrow."

For researchers interested in this pairing, resources on sermorelin, ipamorelin, and CJC-1295 dosing provide useful context on how dosing ratios are being structured. A related product reference for lab-grade material is the CJC-1295 IPA 10mg formulation used in current research settings.

Beyond ipamorelin, 2026 protocols are increasingly incorporating Tesamorelin, an FDA-approved GHRH analog with a documented record from HIV lipodystrophy trials. That clinical history provides safety signals that pure research peptides lack. Researchers exploring this avenue can review the Tesamorelin and CJC-1295 combination framework, which positions both analogs within the broader GHRH class. Multi-peptide blends, such as those covered in Tesamorelin, CJC-1295, and ipamorelin 12mg blend protocols, are also appearing in emerging metabolic research designs.

Common 2026 stacking configurations:

  • CJC‑1295 (no DAC) + ipamorelin: nightly, circadian-timed
  • CJC‑1295 (with DAC) + ipamorelin: weekly CJC, daily ipamorelin
  • CJC‑1295 + Tesamorelin + ipamorelin: multi-target metabolic protocols
  • CJC‑1295 + AOD-9604 blends: body composition-focused research designs

What the Evidence Actually Shows, and Where It Falls Short

What the Evidence Actually Shows, and Where It Falls Short

Honest assessment of the evidence base matters here. IGF-1 elevation following CJC‑1295 administration is consistently documented across multiple study designs. That finding is robust. What remains less clear is the translation of that IGF-1 rise into hard clinical endpoints.

What is reasonably supported:

  • Dose-dependent increases in IGF-1 and GH
  • Improved lean mass markers in some body composition studies
  • Potential benefits in tissue recovery research contexts, particularly around collagen synthesis pathways
  • Modest improvements in sleep quality linked to nocturnal GH pulsatility

What remains speculative or under-studied:

  • Long-term glucose metabolism effects at fixed clinic doses vs. weight-based trial doses
  • Durability of body composition changes after cycle cessation
  • Comparative efficacy of DAC vs. no-DAC forms on recovery-specific endpoints
  • Safety profile in populations beyond healthy adults and HIV lipodystrophy patients

The gap between weight-based dosing used in clinical trials and the fixed doses common in clinic or biohacking settings is a persistent methodological problem. Most trial data comes from weight-adjusted protocols; most real-world use does not follow that model. Researchers tracking tissue repair research outcomes need to account for this discrepancy when interpreting results.

Lab-based monitoring, specifically IGF-1, fasting glucose, and HbA1c panels, is now considered standard practice in responsible 2026 protocol designs, particularly for cycles exceeding eight weeks.

Conclusion

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show points toward a maturing field that is moving beyond simple GH elevation as a goal. The DAC form suits sustained, low-frequency dosing with structured washout; the no-DAC form fits circadian-aligned, pulsatile strategies. Combination stacking with ipamorelin and Tesamorelin is now the research norm rather than the exception.

Actionable next steps for researchers and clinicians:

  1. Select the CJC‑1295 variant based on dosing frequency needs and desensitization tolerance, not convenience alone.
  2. Pair with ipamorelin for synergistic GH pulse amplification with a cleaner hormonal side-effect profile.
  3. Establish baseline IGF-1, fasting glucose, and HbA1c before any cycle begins.
  4. Build washout periods into DAC-based protocols, typically four to six weeks after an eight-to-twelve-week active phase.
  5. Interpret body composition and recovery outcomes against trial-dosing literature with appropriate caution given the fixed-dose gap.

The evidence base will sharpen as more combination protocols generate structured outcome data. Until then, disciplined lab monitoring and conservative cycle design remain the most defensible approach.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cjc-1295-with-and-without-dac-in-emerging-recovery-and-metabolic-research-what-2-1.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-02 13:04:042026-09-02 13:04:04CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show
CJC-1295 With Ipamorelin: How Researchers Model GH Pulsatility and Recovery Endpoints

CJC-1295 With Ipamorelin: How Researchers Model GH Pulsatility and Recovery Endpoints

August 13, 2026/0 Comments/in Uncategorized/by

Growth hormone does not flow in a steady stream. It fires in discrete pulses, a physiological rhythm that governs tissue repair, metabolic signaling, and recovery. That single fact explains why CJC-1295 with ipamorelin: how researchers model GH pulsatility and recovery endpoints has become one of the most discussed combination frameworks in peptide research circles in 2026.

The two compounds are not interchangeable. They target different receptors, carry different half-lives, and produce different waveforms. Their value lies precisely in that difference.

Key Takeaways

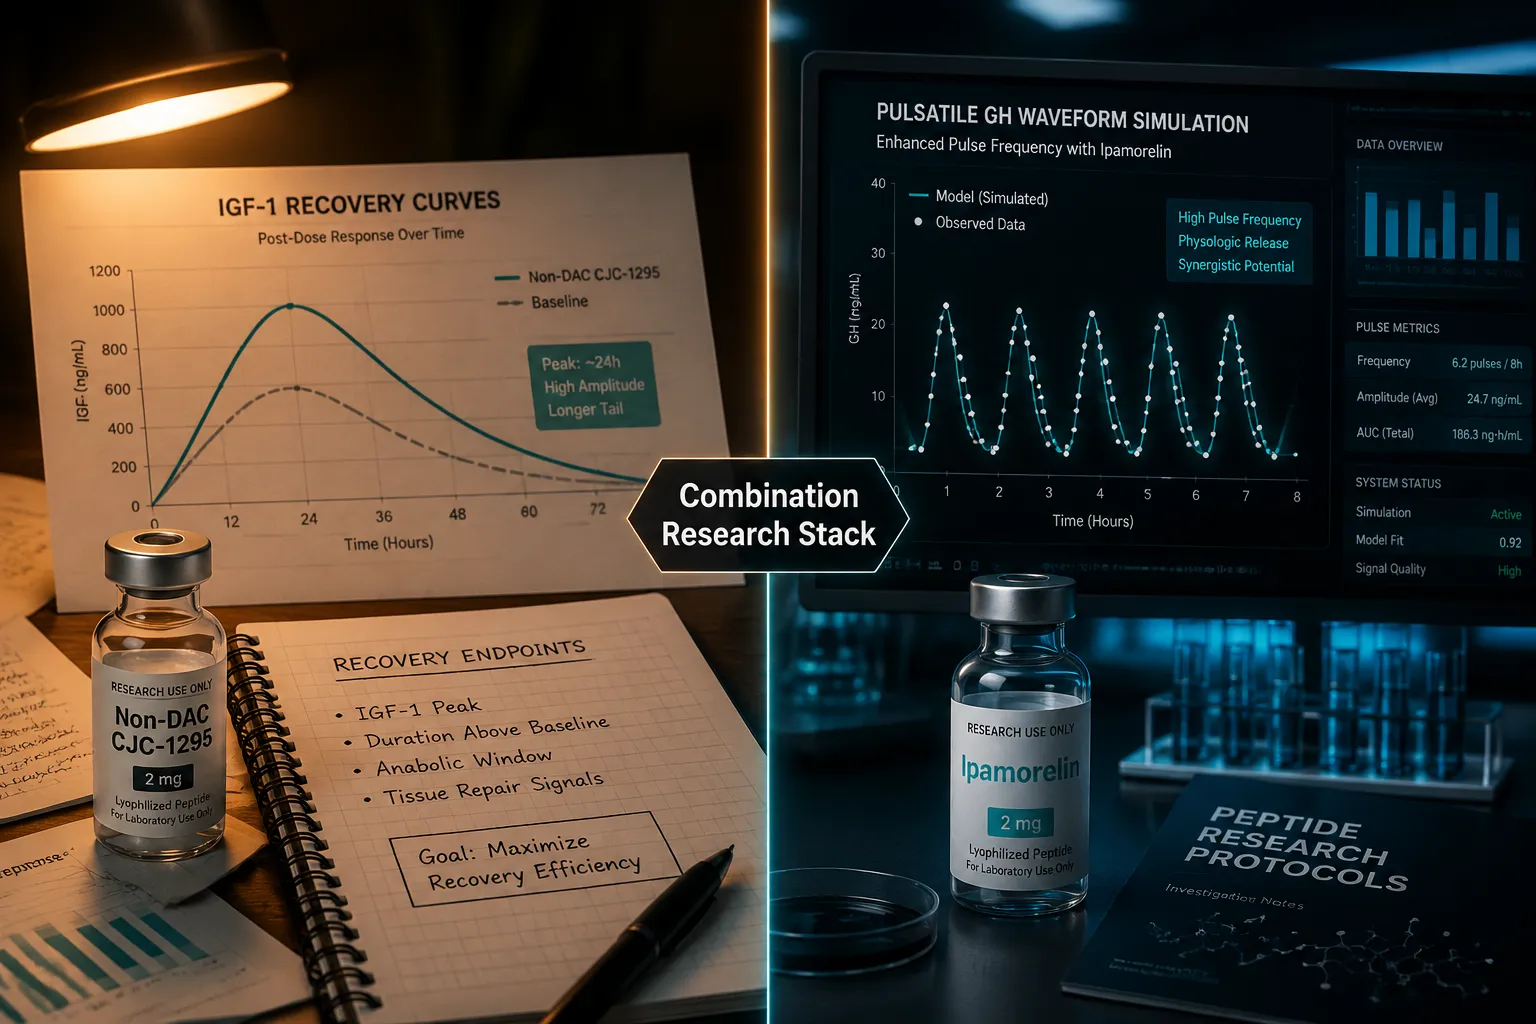
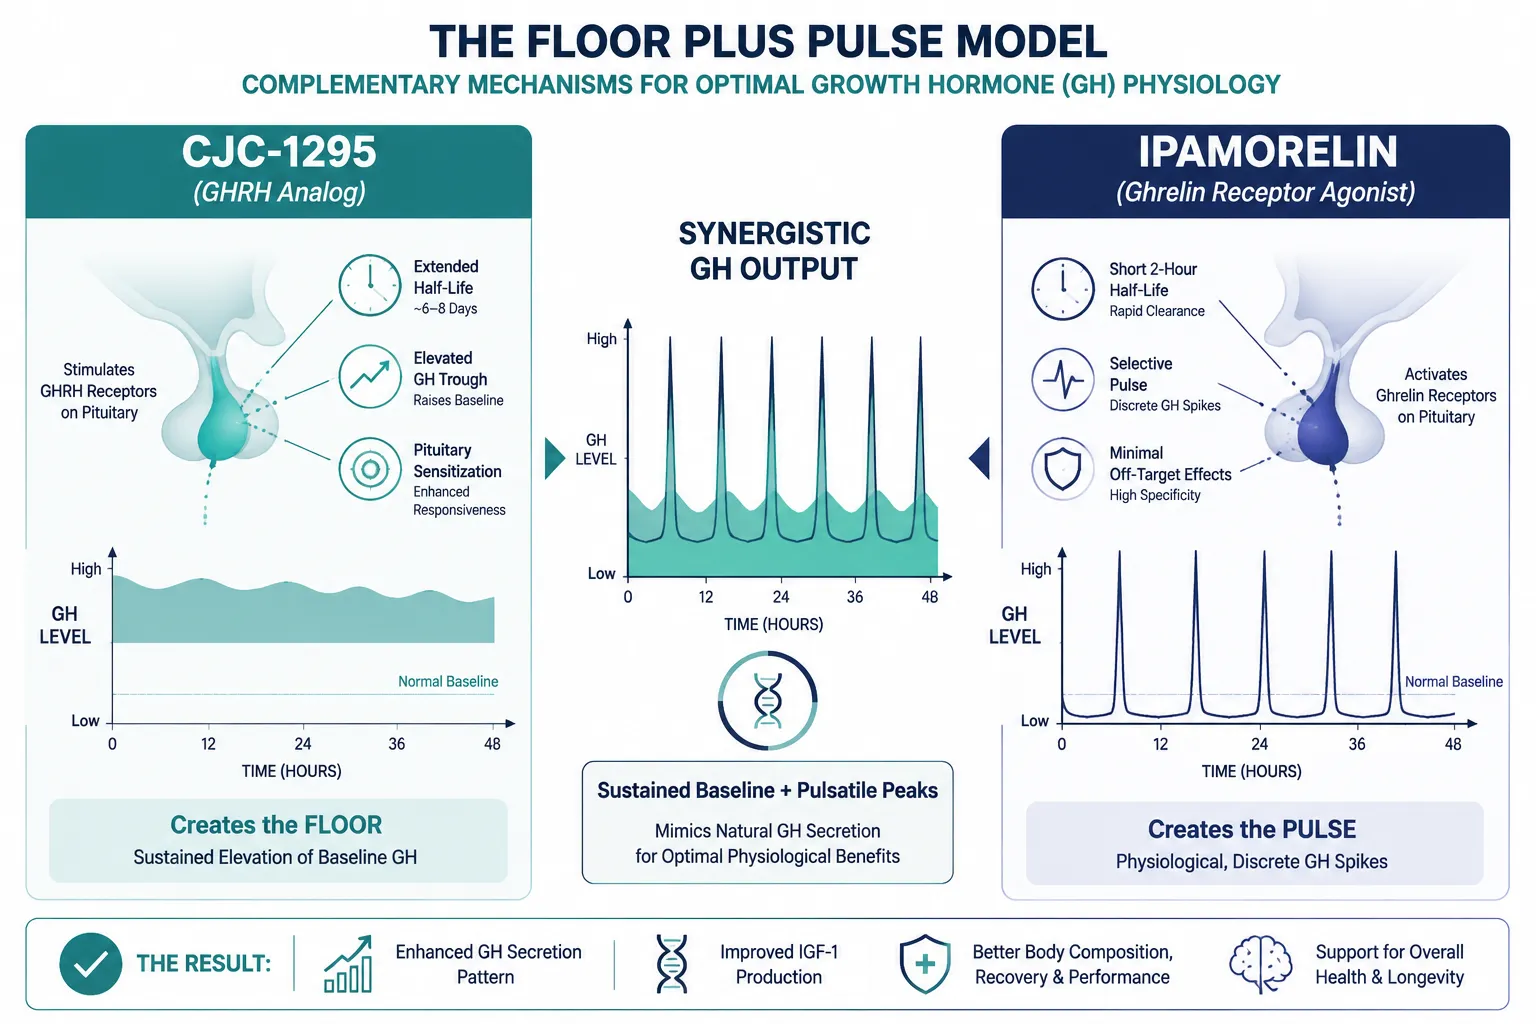
  • CJC-1295 raises the GH baseline ("floor") by acting on GHRH receptors; ipamorelin adds sharp, discrete pulses via ghrelin receptor activation.
  • Together they are modeled as a "floor + pulse" system, with reported 3- to 5-fold increases in modeled GH pulse amplitude.
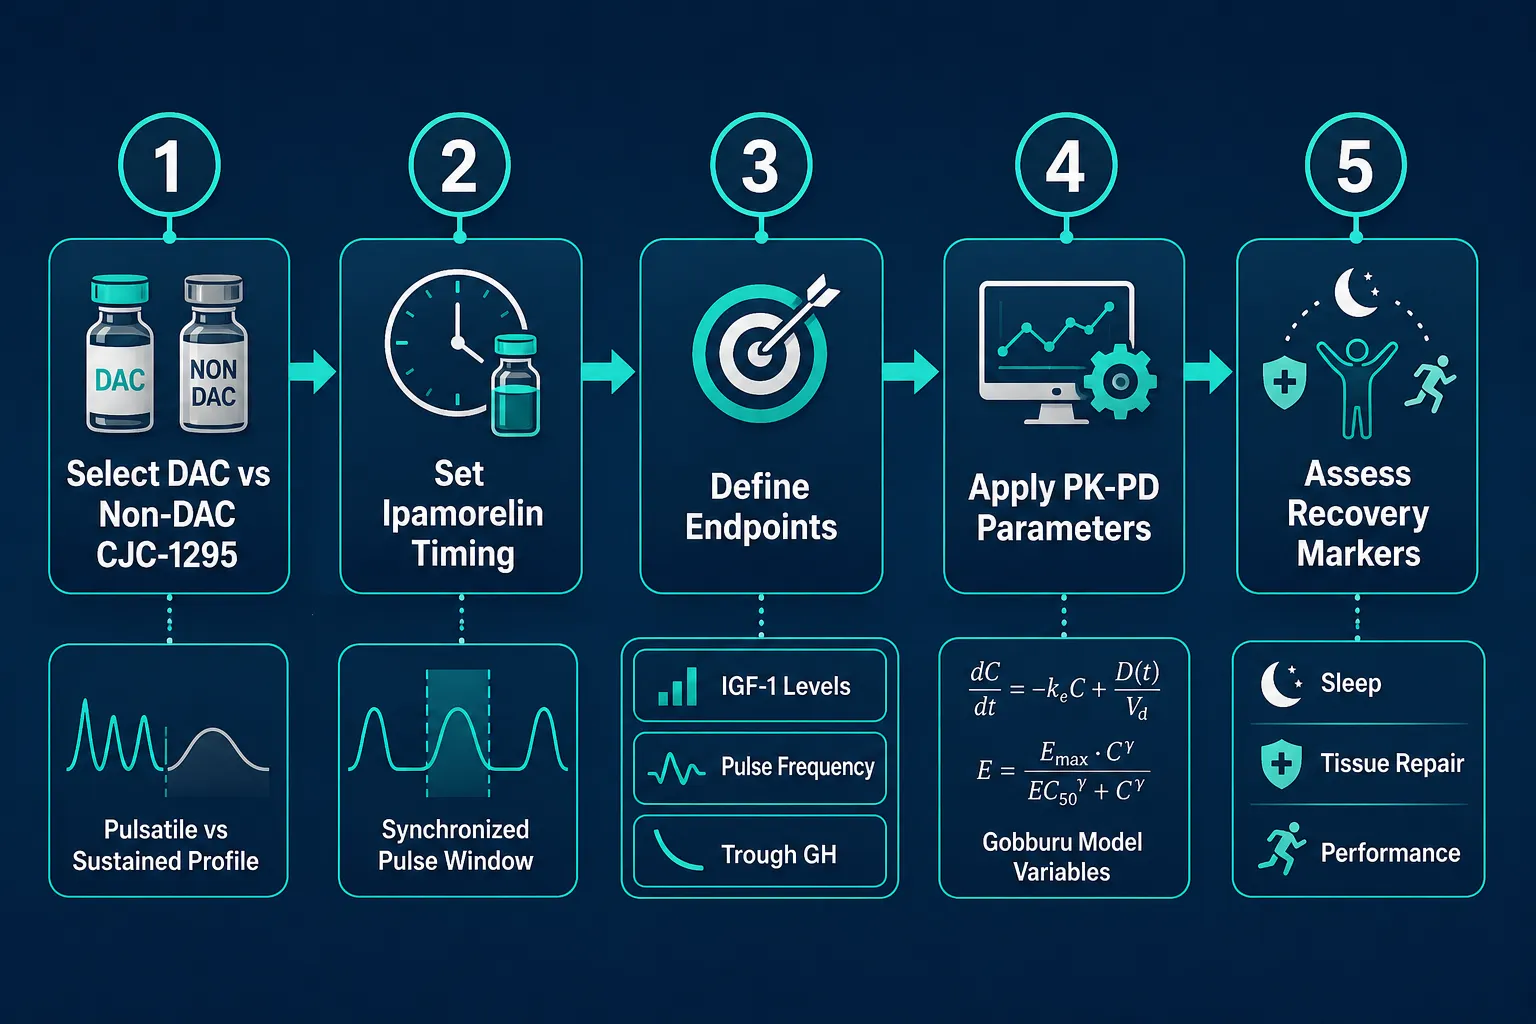
  • Endpoint selection, trough GH, mean GH, IGF-1, pulse frequency, receptor resensitization time, determines how recovery is quantified in experimental designs.
  • The choice between DAC and non-DAC CJC-1295 is central to whether the resulting GH profile is pulsatile or sustained.
  • As of 2026, evidence for the combination remains largely mechanistic; few formal clinical outcome trials exist.

The Mechanistic Case for Combining CJC-1295 and Ipamorelin

The Mechanistic Case for Combining CJC-1295 and Ipamorelin

The rationale for pairing these two compounds starts at the receptor level. CJC-1295 is a modified GHRH analog that binds to GHRH receptors on pituitary somatotrophs. It elevates both trough and mean GH concentrations while preserving the natural pulsatile architecture of GH secretion, a feature that distinguishes it from continuous infusion models. Researchers describe this as establishing the GH "floor."

Ipamorelin operates through a completely different pathway. As a highly selective ghrelin receptor (GHS-R1a) agonist, it triggers short, discrete GH pulses. Its plasma half-life of approximately two hours makes it well-suited for time-locked pulse modeling. Critically, ipamorelin shows minimal off-target endocrine effects, it does not meaningfully elevate cortisol or prolactin at research-relevant doses, which simplifies endpoint interpretation.

Why combine them? Each compound amplifies what the other cannot do alone:

Compound Receptor Target Primary Effect Half-Life
CJC-1295 (non-DAC) GHRH receptor Elevated GH trough, sustained sensitization ~30 minutes active window
CJC-1295 (with DAC) GHRH receptor Prolonged GH elevation, blunted pulsatility ~8 days
Ipamorelin GHS-R1a (ghrelin receptor) Sharp discrete GH pulses ~2 hours

"The combination is modeled as floor-plus-pulse physiology, CJC-1295 primes the pituitary while ipamorelin triggers the release event."

For researchers interested in how different GHRH-mimetic profiles shape study outcomes, the comparison of tesa, ipamorelin, and CJC-1295 with DAC provides additional mechanistic context.

Modeling GH Pulsatility and Recovery Endpoints: Design Considerations

Modeling GH Pulsatility and Recovery Endpoints: Design Considerations

When researchers frame studies around CJC-1295 with ipamorelin: how researchers model GH pulsatility and recovery endpoints, several design variables must be resolved before data collection begins.

DAC vs. Non-DAC: A Critical Fork in Pulsatility Modeling

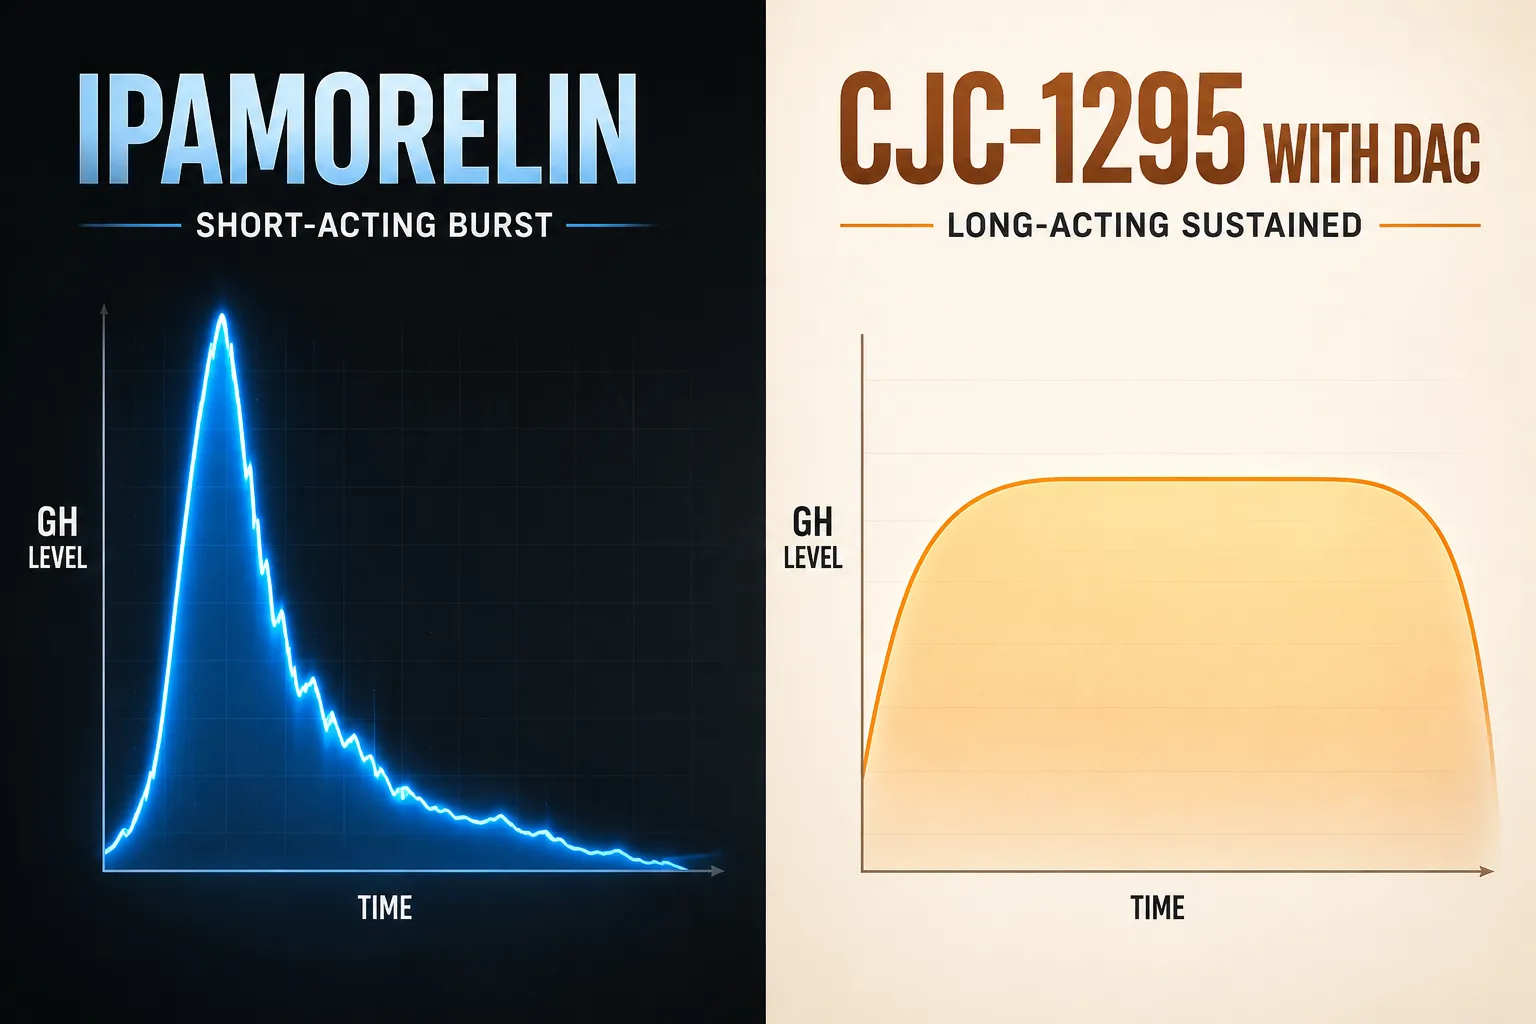
The Drug Affinity Complex (DAC) modification extends CJC-1295's half-life to approximately eight days by binding reversibly to albumin. This creates a sustained GH elevation but flattens the pulsatile profile. When investigators specifically want to study pulsatile GH dynamics, they use non-DAC CJC-1295 (also called Mod GRF 1-29), which produces a shorter, cleaner activation window that pairs more naturally with ipamorelin's pulse timing.

For a deeper look at the DAC variant's pharmacology, the CJC-1295 with DAC deeper dive resource outlines the structural and kinetic distinctions relevant to study design.

Quantitative PK-PD Parameters

Pharmacokinetic-pharmacodynamic (PK-PD) modeling for ipamorelin, grounded in foundational work by Gobburu and colleagues, provides quantitative parameters that researchers now use to simulate GH pulsatility and recovery trajectories. These parameters include:

  • Peak GH concentration following a defined dose
  • Time to peak relative to administration
  • Area under the GH curve (AUC) as a proxy for total GH exposure
  • Receptor resensitization time, the interval before the next pulse can be reliably triggered

When CJC-1295 is added to the model, the pituitary is already sensitized, which means ipamorelin-triggered pulses produce 3- to 5-fold greater amplitude than ipamorelin alone in modeled outputs.

Recovery Endpoints Researchers Track

Recovery-focused experimental designs typically monitor several endpoints in parallel:

  • IGF-1 levels, the downstream hepatic marker most consistently elevated by sustained GH signaling
  • Trough GH, the baseline between pulses, elevated by CJC-1295
  • Pulse frequency and amplitude, quantified via serial GH sampling
  • Surrogate recovery markers, including sleep architecture, lean tissue preservation, and wound-healing proxies in preclinical models

Researchers exploring CJC-1295 and ipamorelin dosage frameworks will find that timing recommendations in 2026 research guides are explicitly structured around these pulsatility and recovery modeling goals rather than arbitrary schedules.

Current Limitations and the State of Evidence in 2026

Current Limitations and the State of Evidence in 2026

Expert consensus in 2026 is clear: the evidence base for CJC-1295 with ipamorelin: how researchers model GH pulsatility and recovery endpoints remains largely mechanistic and extrapolative. The combination framework draws heavily on classic peer-reviewed GH secretagogue literature, with more recent resources primarily repackaging those data for combination modeling contexts.

Formal clinical outcome trials are sparse. Most published data address single-compound pharmacology, and the "floor + pulse" combination model is largely constructed from:

  1. Individual compound PK-PD studies
  2. Mechanistic inference from GH physiology research
  3. Preclinical and small-sample human secretagogue studies

This does not diminish the research utility of the framework. It does mean that investigators should distinguish between modeled endpoints (simulated from PK-PD parameters) and measured outcomes (from controlled trials). Conflating the two is the most common methodological error in secondary literature on this topic.

Researchers building multi-compound GH-axis protocols may also find value in reviewing tesa and ipamorelin combination protocols for GH-axis modulation, which addresses overlapping design challenges.

For those working with stacked secretagogue approaches, the sermorelin, ipamorelin, and CJC-1295 research stack overview provides a comparative framework across three commonly studied GHRH-pathway compounds.

Conclusion

The pairing of CJC-1295 and ipamorelin in research settings is not arbitrary. It reflects a deliberate attempt to reconstruct physiologically relevant GH pulsatility, elevating the trough with one compound while generating discrete, amplified pulses with the other. The resulting "floor + pulse" model offers a structured framework for studying recovery endpoints including IGF-1 response, pulse amplitude, and tissue-repair surrogates.

Actionable next steps for researchers:

  • Clarify whether DAC or non-DAC CJC-1295 fits the pulsatility profile the study requires before selecting a protocol.
  • Define recovery endpoints precisely, IGF-1, trough GH, pulse frequency, and resensitization time each require different sampling designs.
  • Anchor modeled outputs to published PK-PD parameters rather than anecdotal dosing guides.
  • Distinguish mechanistic models from clinical outcome evidence when interpreting or reporting results.
  • Review multi-compound blend research, such as the tesa, AOD-9604, CJC-1295, and ipamorelin 12mg blend, to understand how researchers extend single-axis models into broader metabolic frameworks.

The science is promising. The rigor with which endpoints are defined will determine whether that promise translates into meaningful data.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-ipamorelin-how-researchers-model-gh-pulsatility-and-recovery-endpo.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-13 13:04:452026-08-13 13:04:45CJC-1295 With Ipamorelin: How Researchers Model GH Pulsatility and Recovery Endpoints
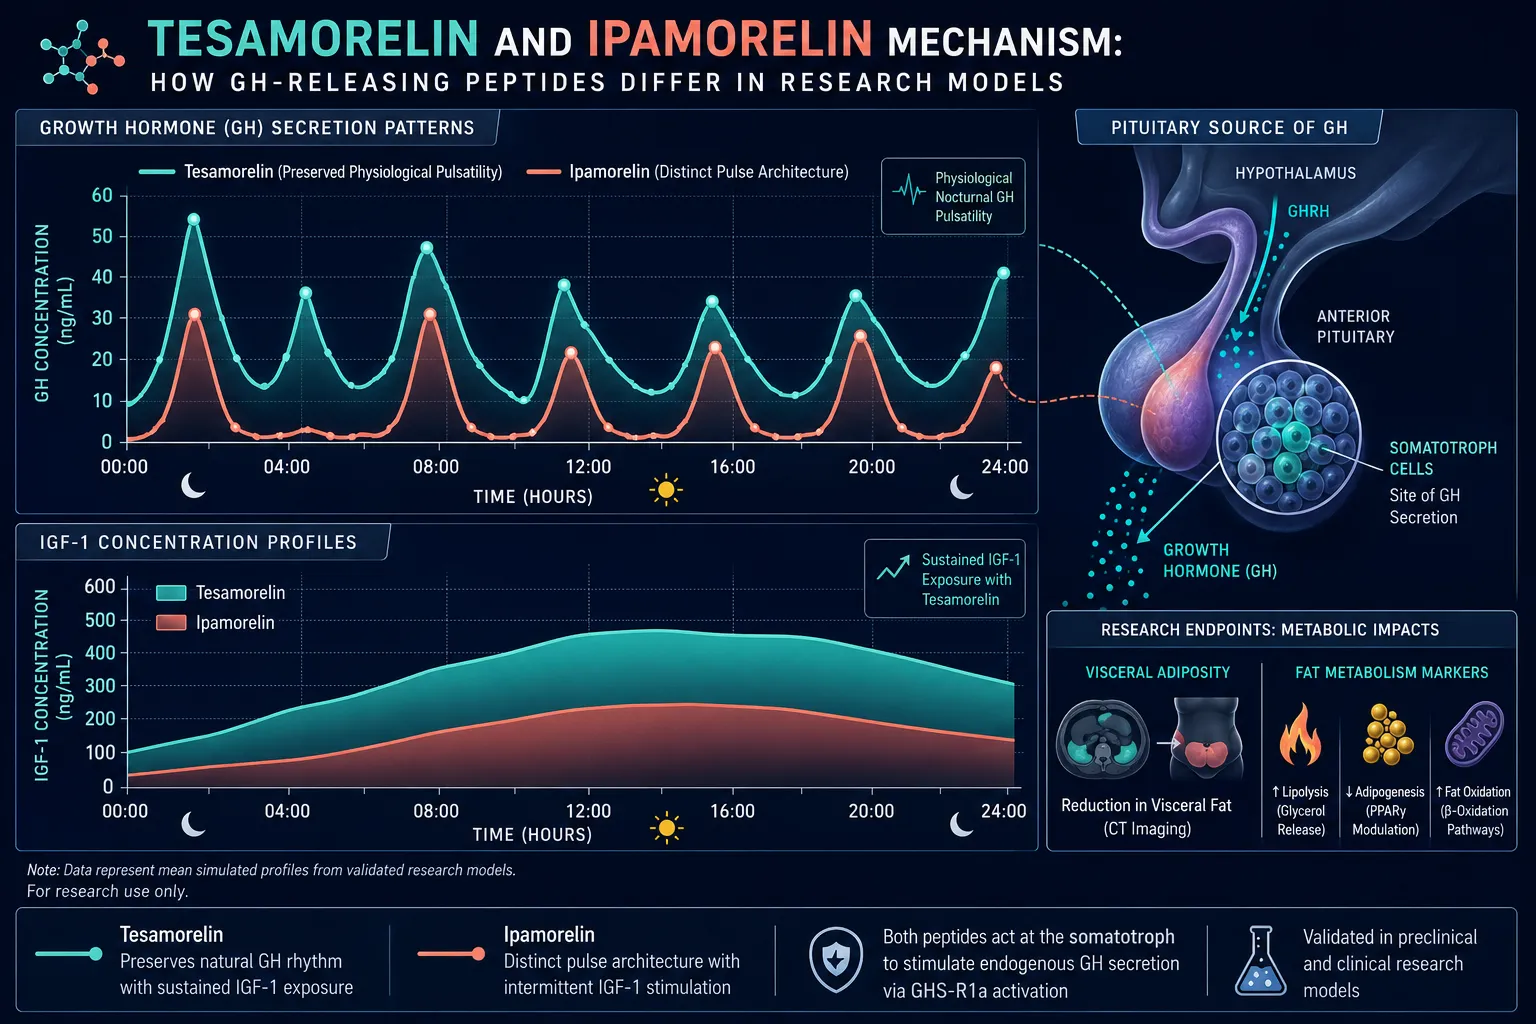
Tesamorelin and Ipamorelin Mechanism: How GH-Releasing Peptides Differ in Research Models

Tesamorelin and Ipamorelin Mechanism: How GH-Releasing Peptides Differ in Research Models

August 11, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay (≤42 chars): 'GH Peptides: Tesamorelin vs Ipamorelin' in crisp white bold sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge. Background: stunning macro editorial photograph of two distinct molecular helix structures side by side, rendered in glowing teal and amber on a dark scientific gradient background, laboratory aesthetic with soft bokeh light particles, magazine cover quality, high contrast, biotech editorial style.","content":["Flat vector infographic illustration in landscape format (1536×1024): two distinct signaling pathway diagrams side by side on a clean white background, left pathway labeled 'GHRH Receptor' with cAMP and PKA cascade shown as clean arrows in deep blue tones, right pathway labeled 'Ghrelin Receptor' with Gq/PLC/IP3 and calcium wave icons in warm amber tones. Bold minimal icons, short 2-3 word labels only, bright clinical palette, save-worthy scientific education style, no tables, generous 8% safe margins.","Editorial split-screen landscape (1536×1024): left half shows a stylized pituitary gland illustration with rhythmic pulse wave lines in cool blue representing pulsatile GH release from GHRH stimulation; right half shows a warm amber-toned illustration of ghrelin receptor activation with calcium ion burst and downstream metabolic fat-cell icons. High-contrast dividing line down center, clean biotech magazine aesthetic, minimal 3-word labels only, no pricing or tables, varied composition from section 1.","Cinematic editorial photograph in landscape format (1536×1024): a focused female South Asian researcher in her 30s in a bright modern laboratory, examining a glowing digital screen displaying IGF-1 and GH pulse graphs with two distinct waveform patterns highlighted in blue and orange. Clean white lab coat, shallow depth of field, natural daylight from large windows, warm-cool contrast lighting, research-focused composition, magazine quality, no tables, 8% safe margins on any overlay text.","content":["prompt1","prompt2","prompt3"]}

Professional landscape hero image () with a reading "Tesamorelin and Ipamorelin Mechanism: How…". CRITICAL TYPOGRAPHY RULES:

Two peptides. One shared goal, stimulating growth hormone release. Yet the Tesamorelin and Ipamorelin mechanism diverges at the receptor level in ways that produce measurably different downstream effects in research models. Understanding that divergence is not a minor academic detail; it shapes how researchers design experiments, interpret IGF-1 data, and evaluate fat-related endpoints.

Key Takeaways

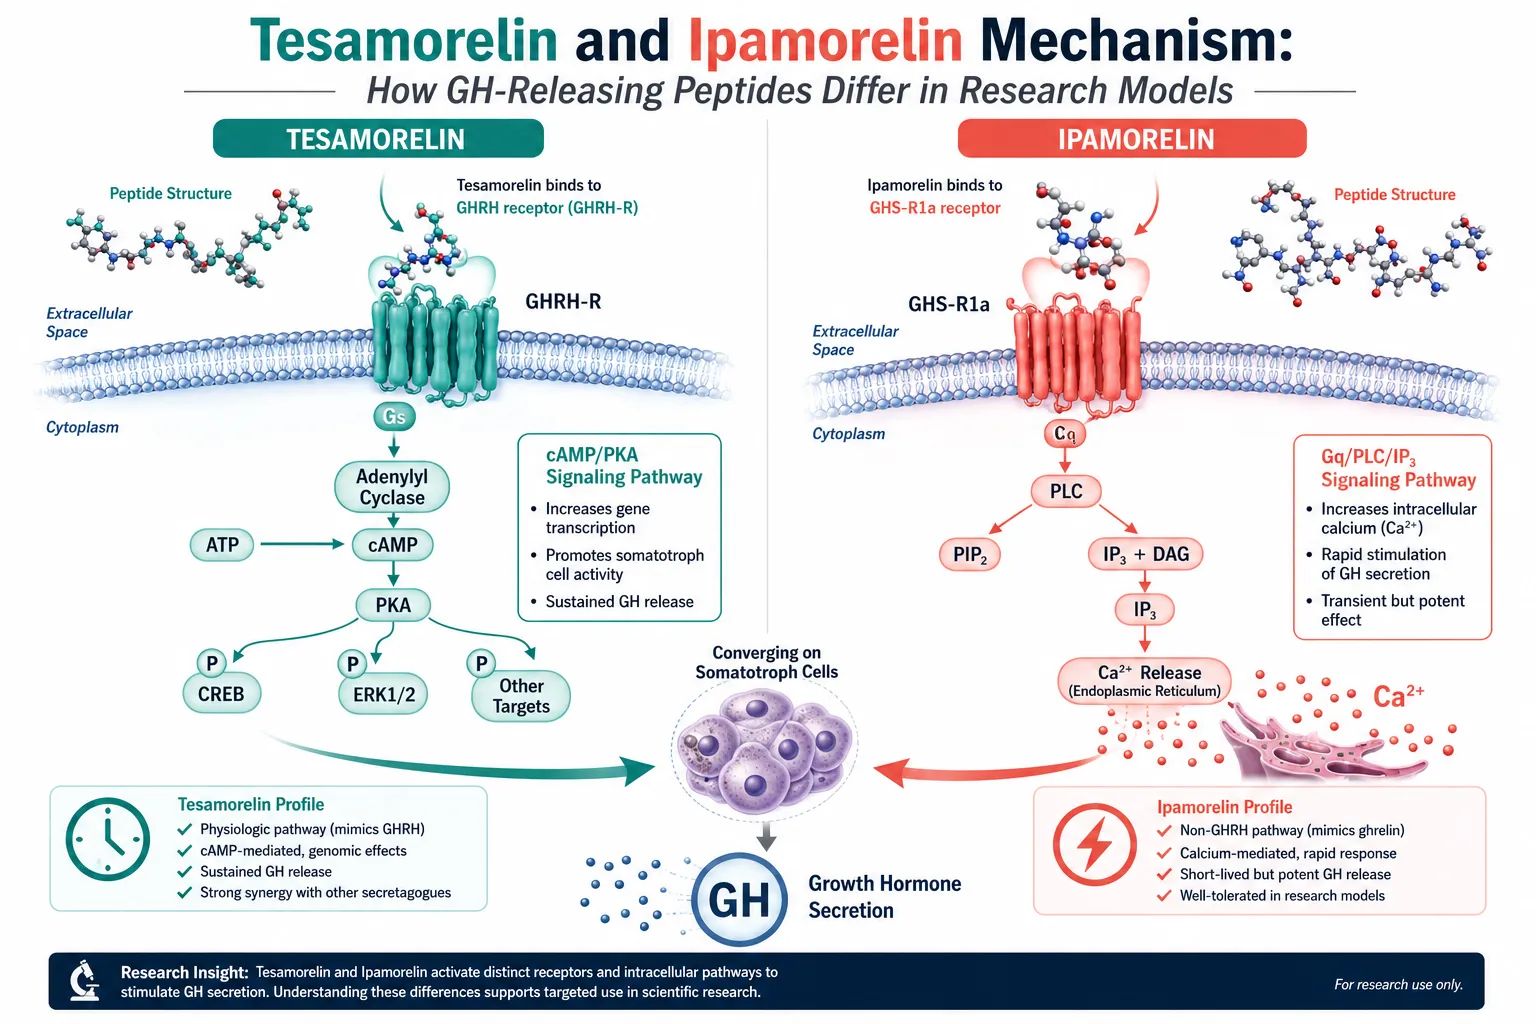
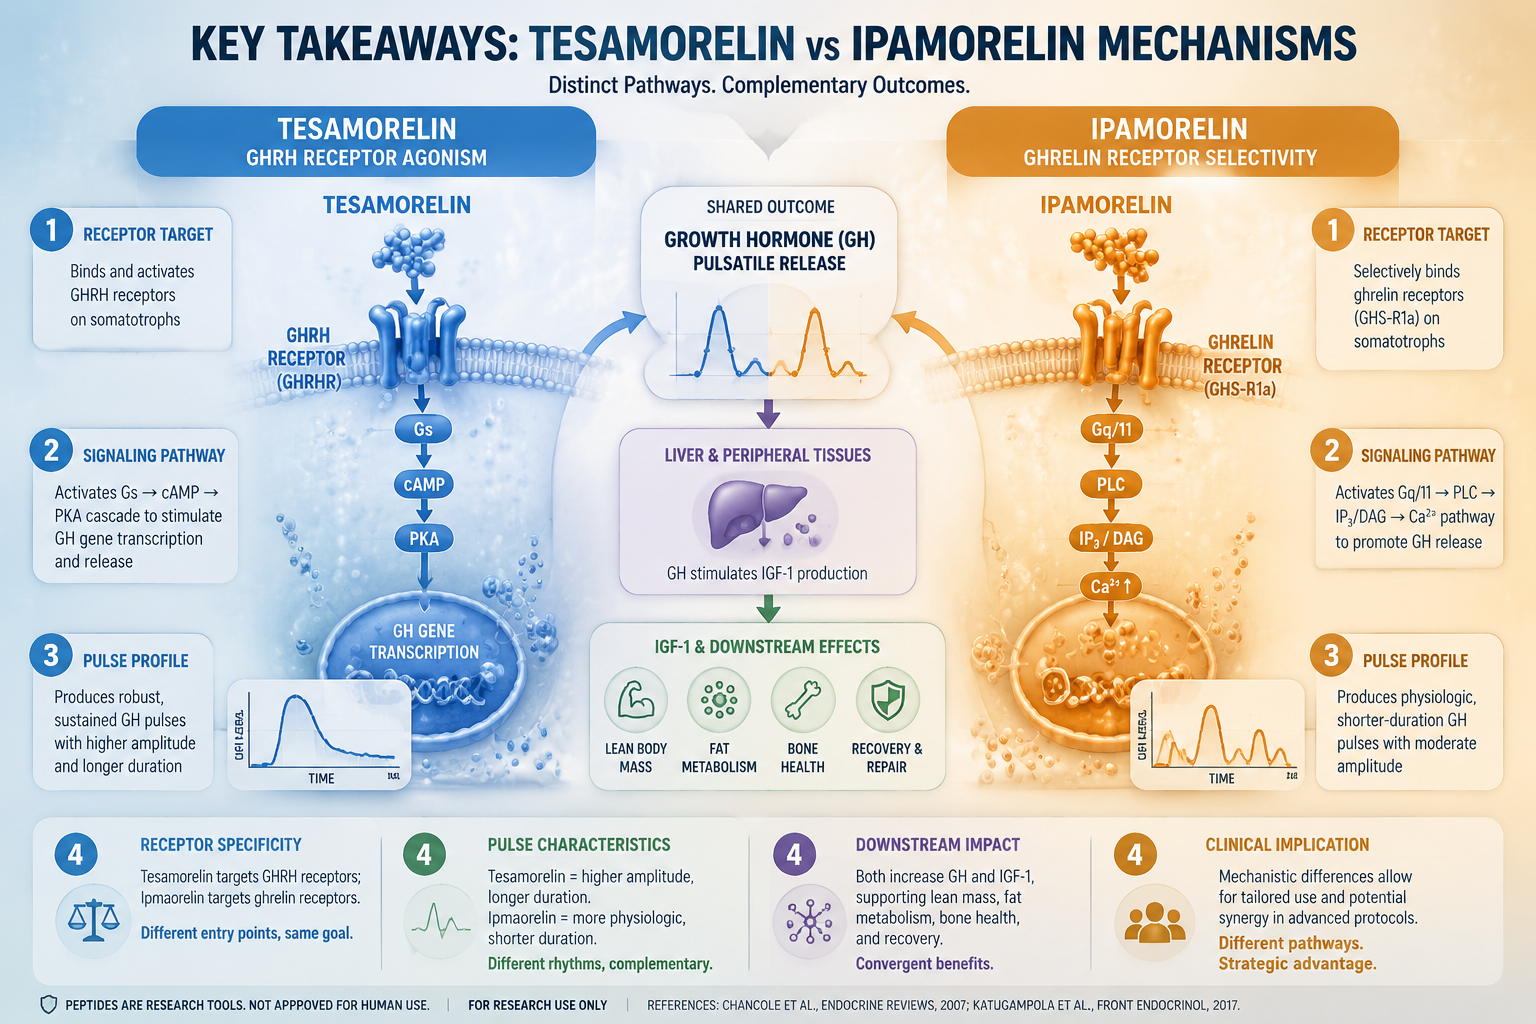
  • Tesamorelin is a GHRH analog that activates the GHRH receptor via a cAMP/PKA signaling cascade, closely mimicking endogenous hypothalamic input.
  • Ipamorelin is a ghrelin mimetic that activates the GHS-R1a receptor through a Gq/PLC/IP3-calcium pathway, a mechanistically distinct route.
  • The two pathways produce different pulsatility profiles and downstream IGF-1 responses in preclinical models.
  • Tesamorelin has a documented record in visceral fat reduction research; Ipamorelin is studied primarily for clean GH pulse amplification with minimal off-target hormone effects.
  • Combining both peptides in research designs may engage complementary axes of GH secretion, a rationale explored in multi-peptide blend studies.

Key Takeaways

Core Receptor Biology: Where the Pathways Split

The Tesamorelin and Ipamorelin mechanism comparison begins at the receptor binding step, and the differences are fundamental.

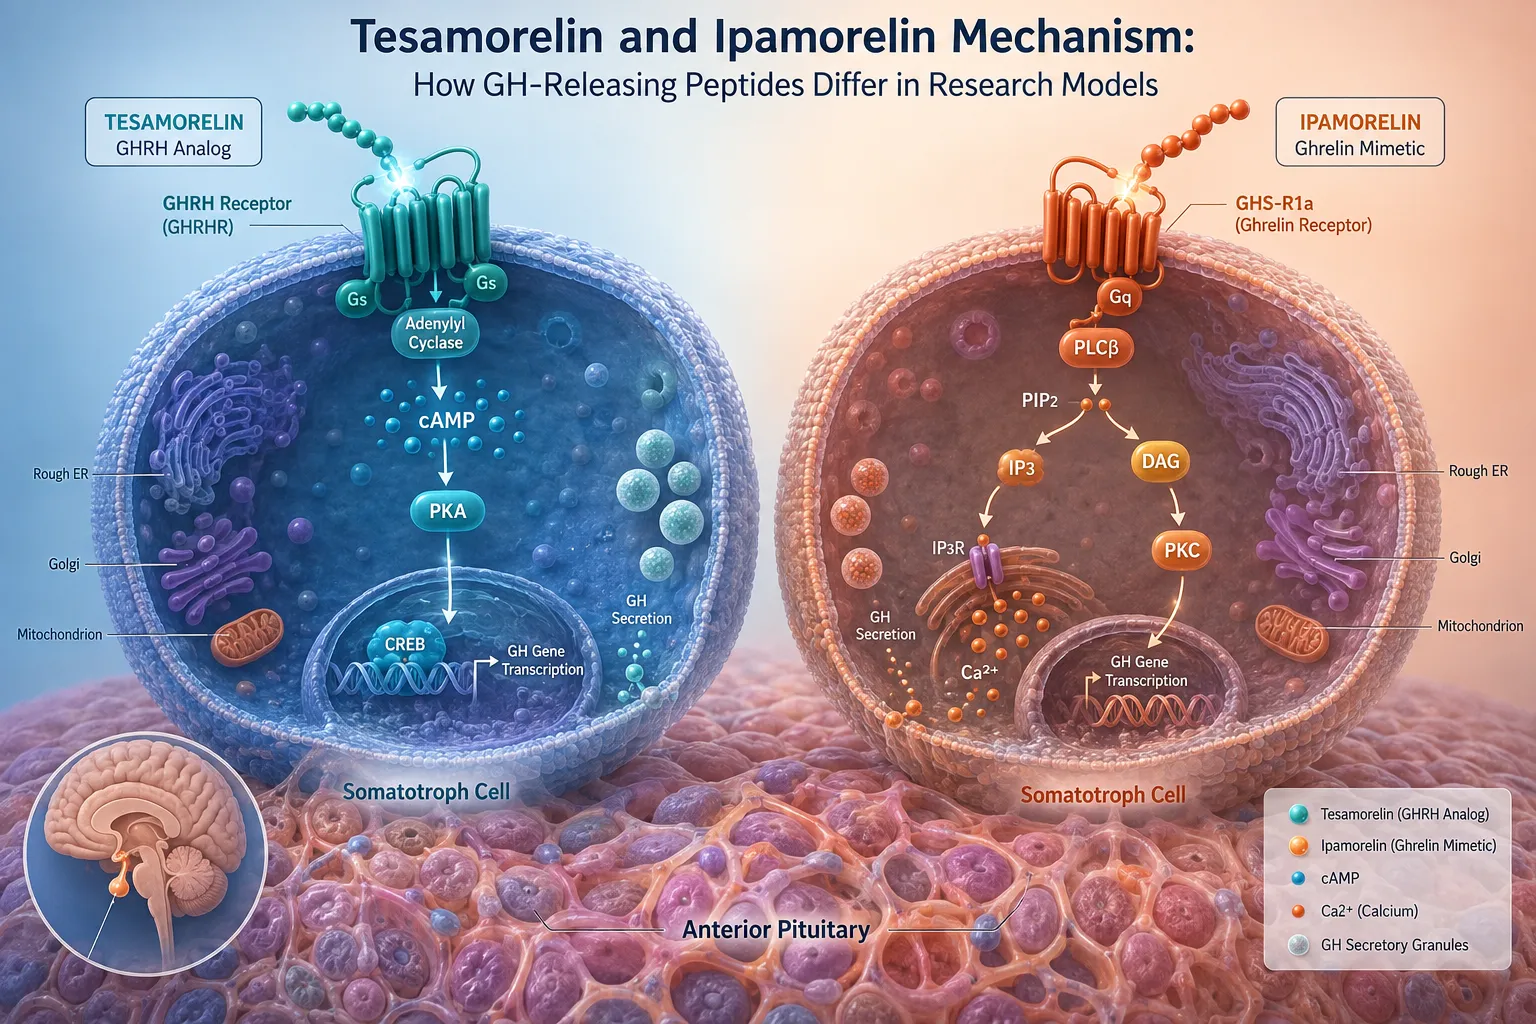
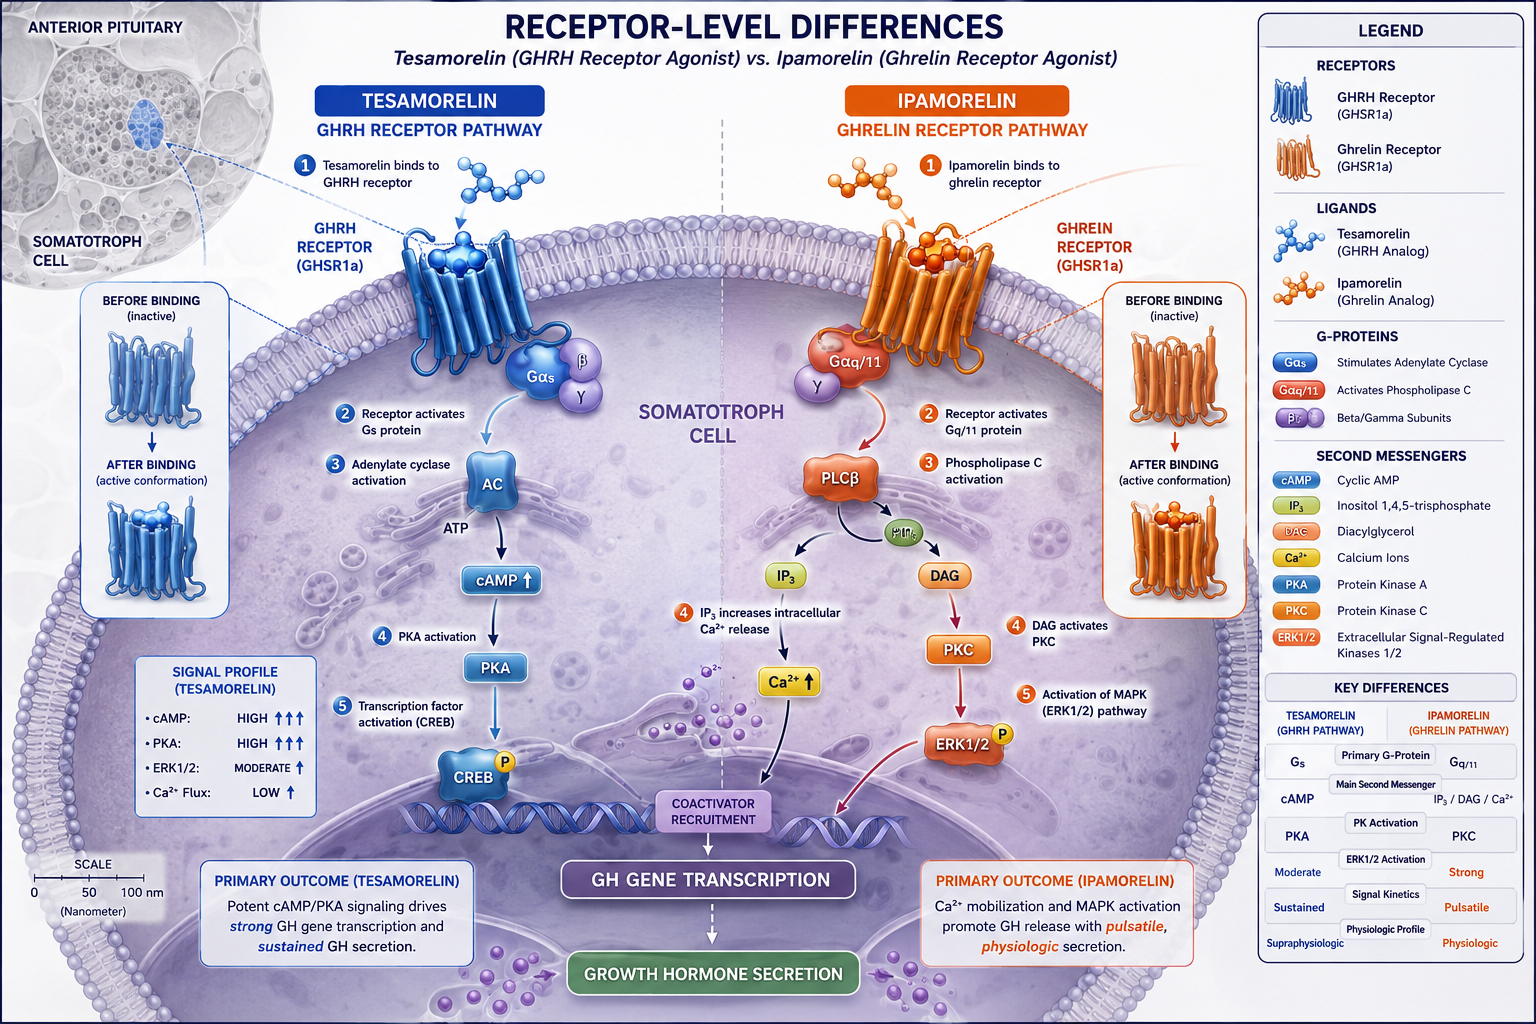
Tesamorelin is a stabilized synthetic analog of growth hormone-releasing hormone (GHRH). It binds selectively to the GHRH receptor (GHRHR) on somatotroph cells in the anterior pituitary. Activation of GHRHR couples to a Gs protein, which stimulates adenylyl cyclase to elevate intracellular cyclic AMP (cAMP). Elevated cAMP activates protein kinase A (PKA), which then phosphorylates transcription factors and ion channels that drive GH synthesis and secretion. This pathway closely mirrors the body's own hypothalamic signal.

Ipamorelin, by contrast, is a selective ghrelin receptor agonist, specifically targeting the growth hormone secretagogue receptor type 1a (GHS-R1a). This receptor couples to a Gq protein rather than Gs. Gq activates phospholipase C (PLC), which cleaves PIP2 into inositol trisphosphate (IP3) and diacylglycerol (DAG). IP3 triggers calcium release from intracellular stores, and the resulting calcium surge drives GH exocytosis from somatotroph granules.

Feature Tesamorelin Ipamorelin
Receptor target GHRHR GHS-R1a
G-protein coupling Gs Gq
Second messenger cAMP / PKA IP3 / Ca²⁺
Endogenous analog GHRH Ghrelin
Primary research focus Visceral fat, IGF-1 GH pulse amplitude

For a broader look at how these and related peptides fit into GH-axis research design, the article on Tesamorelin and Ipamorelin peptides: mechanism, synergy, and growth hormone research design provides useful context.

Pulsatility, IGF-1 Profiles, and Fat-Related Endpoints

Pulsatility, IGF-1 Profiles, and Fat-Related Endpoints

The signaling difference between cAMP/PKA and Gq/PLC/IP3-Ca²⁺ is not merely biochemical trivia. It translates into distinct patterns of GH secretion that researchers observe in animal models.

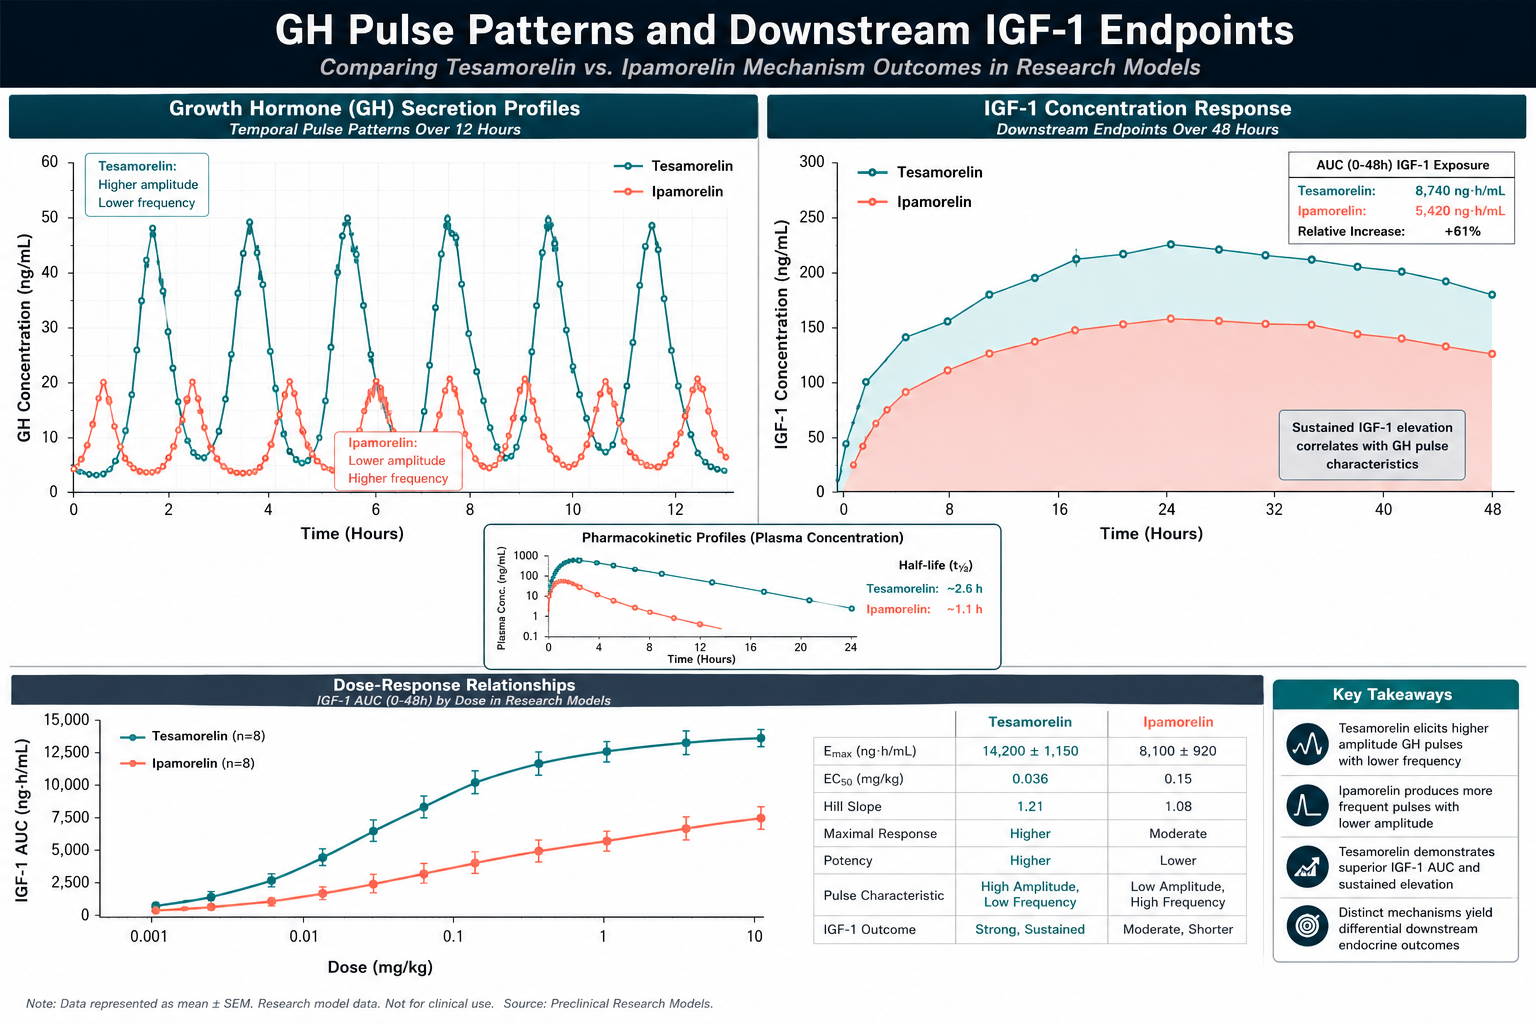
Pulsatile GH release is a physiologically critical feature. The pituitary does not secrete GH continuously; it releases it in discrete pulses. Tesamorelin, acting through the GHRH receptor, amplifies the natural pulsatile rhythm because it reinforces the same hypothalamic timing signal. Research models show that GHRH analogs tend to preserve the episodic architecture of GH release rather than flattening it into a tonic pattern.

Ipamorelin's ghrelin-receptor pathway adds a complementary but distinct stimulus. GHS-R1a activation can trigger GH release independently of the GHRH clock, effectively amplifying pulse height without necessarily altering pulse frequency in the same way. Importantly, Ipamorelin is noted in research for its selectivity, it does not significantly stimulate cortisol, prolactin, or ACTH at research-relevant concentrations, unlike older GH secretagogues such as GHRP-2. This makes it a cleaner tool for isolating GH-specific effects.

IGF-1 downstream effects differ accordingly. Because Tesamorelin closely mimics endogenous GHRH input, it tends to produce sustained IGF-1 elevation in models where the GH axis is intact. This sustained IGF-1 response is mechanistically linked to the visceral fat reduction endpoints that have made Tesamorelin one of the more studied GHRH analogs. Researchers interested in the science behind these effects can explore what Tesamorelin is and the science behind it for additional background.

Ipamorelin's IGF-1 profile in models tends to be robust but tied more directly to pulse amplitude than to tonic elevation, reflecting its role as a pulse amplifier rather than a rhythm synchronizer.

Key distinction: Tesamorelin drives GH secretion by reinforcing the hypothalamic clock signal. Ipamorelin drives it by pulling a separate calcium-dependent trigger at the somatotroph level. Both increase GH output, but through non-overlapping molecular events.

Research Design Implications: Choosing Between or Combining Both

Research Design Implications: Choosing Between or Combining Both

Understanding the Tesamorelin and Ipamorelin mechanism difference has direct implications for how researchers structure their protocols.

When to study each compound separately:

  • Use Tesamorelin when the research question centers on GHRH-receptor signaling, visceral adiposity models, or IGF-1-mediated anabolic endpoints.
  • Use Ipamorelin when the goal is to study GHS-R1a pharmacology, clean GH pulse amplification, or selectivity relative to other pituitary hormones.

Rationale for combination approaches:

Because the two peptides act on different receptors through different second-messenger systems, they are not redundant. Activating both GHRHR and GHS-R1a simultaneously can produce additive or potentially synergistic GH release. This dual-axis rationale underlies multi-peptide research blends. Researchers exploring combination formats may find the Tesamorelin, CJC-1295, Ipamorelin 12mg blend dosing resource relevant to experimental design considerations.

For those comparing GHRH-class peptides more broadly, the Sermorelin vs Tesamorelin comparison and the Tesamorelin vs Sermorelin analysis offer additional mechanistic context on how different GHRH analogs behave.

Researchers working across the GH axis may also benefit from reviewing peptide mechanism fundamentals covering GLP-3 Retatrutide, CJC-1295, and MOTS-c to situate GH-releasing peptides within the broader landscape of receptor-level research.

Somatostatin tone matters. Both peptides operate within the context of endogenous somatostatin inhibition. Tesamorelin's efficacy depends partly on the prevailing somatostatin tone in the model; high somatostatin suppression can blunt GHRHR-driven cAMP responses. Ipamorelin is partially resistant to somatostatin inhibition because its calcium-dependent pathway is less sensitive to somatostatin's inhibitory mechanism, giving it a practical advantage in models with elevated somatostatin tone.

Conclusion

The Tesamorelin and Ipamorelin mechanism comparison reveals two peptides that share a functional output, increased GH secretion, while operating through entirely separate receptor systems and intracellular cascades. Tesamorelin drives the cAMP/PKA axis via GHRHR, preserving pulsatile rhythm and supporting sustained IGF-1 elevation relevant to visceral fat endpoints. Ipamorelin activates GHS-R1a through a calcium-dependent Gq pathway, amplifying GH pulse height with high hormonal selectivity.

For researchers working with GH-axis models in 2026, the actionable next steps are clear:

  1. Define the research question first. GHRH-receptor pharmacology calls for Tesamorelin; GHS-R1a selectivity studies call for Ipamorelin.
  2. Consider dual-axis designs when the goal is maximal GH output or when studying synergistic receptor interactions.
  3. Account for somatostatin tone in the model, as it differentially affects each compound's efficacy.
  4. Verify peptide purity before any mechanistic study, receptor-level research requires compounds with confirmed identity and minimal impurities.
https://www.puretestedpeptides.com/wp-content/uploads/2026/08/tesa-and-ipamorelin-mechanism-how-gh-releasing-peptides-differ-in-researc.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-11 13:05:302026-08-11 13:05:30Tesamorelin and Ipamorelin Mechanism: How GH-Releasing Peptides Differ in Research Models
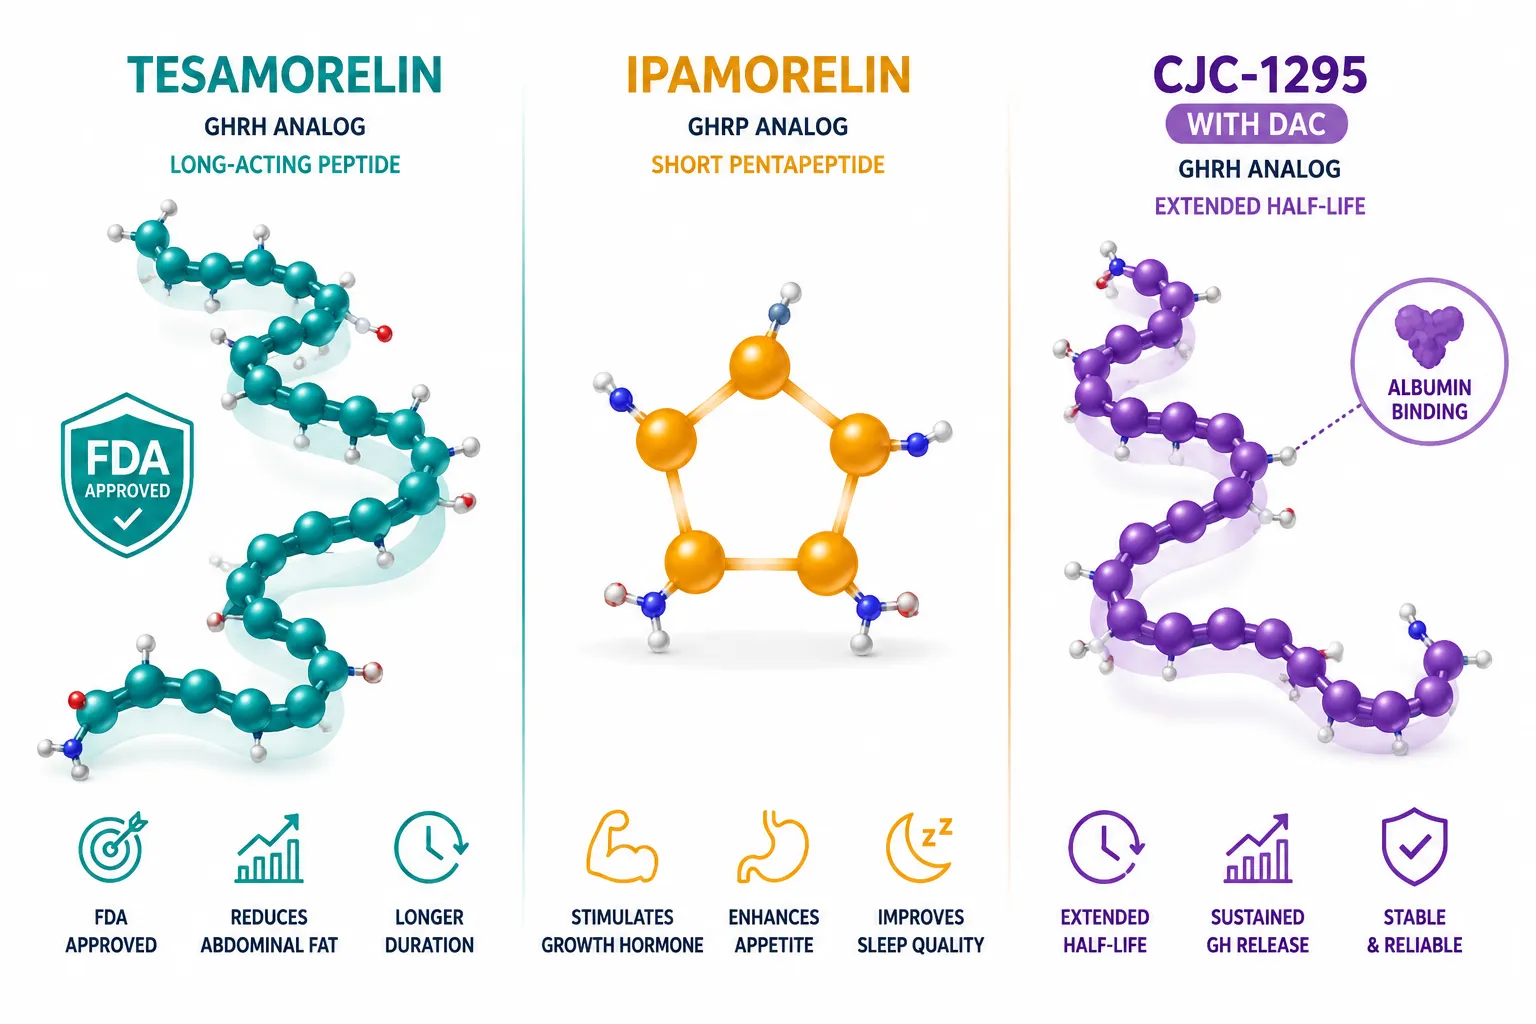
Tesamorelin, Ipamorelin, and CJC-1295 With DAC: How Different GHRH Mimetic Profiles Shape Growth Hormone Study Outcomes

Tesamorelin, Ipamorelin, and CJC-1295 With DAC: How Different GHRH Mimetic Profiles Shape Growth Hormone Study Outcomes

August 6, 2026/0 Comments/in Uncategorized/by

Growth hormone secretagogue research has expanded rapidly, yet fewer than 15% of preclinical labs systematically account for half-life differences when designing GH pulse studies, a gap that skews IGF-1 readouts and muddies cross-study comparisons. Understanding how Tesamorelin, Ipamorelin, and CJC-1295 With DAC: How Different GHRH Mimetic Profiles Shape Growth Hormone Study Outcomes differ at the receptor, pulse, and IGF-1 level is now a foundational requirement for any serious research protocol.

Key Takeaways

  • Tesamorelin is a full-length GHRH analog with FDA-validated receptor fidelity and a short half-life suited to acute pulse studies.
  • Ipamorelin is a selective ghrelin-receptor agonist that drives clean GH pulses without significant cortisol or prolactin co-stimulation.
  • CJC-1295 with DAC uses albumin binding to achieve a 6-8 day effective half-life, fundamentally changing the exposure profile compared to short-acting analogs.
  • Receptor target, pulse shape, and IGF-1 trajectory each vary meaningfully across the three peptides, making protocol design critical.
  • Combination blends can leverage complementary mechanisms, but require careful assay planning to interpret outcomes correctly.

Receptor Targets and Mechanistic Profiles

The first variable that separates these three compounds is where they act.

Tesamorelin is a stabilized synthetic analog of endogenous growth hormone-releasing hormone (GHRH). It binds selectively to the GHRH receptor on pituitary somatotrophs, mimicking the natural signal with high fidelity. Because it preserves the full 44-amino-acid structure of native GHRH, its downstream signaling closely parallels physiological GH release. Researchers exploring what Tesamorelin is and how it works will find it is the closest available analog to endogenous GHRH in terms of receptor engagement.

Ipamorelin operates through an entirely different pathway. As a selective ghrelin receptor (GHS-R1a) agonist, it stimulates GH release via the ghrelin axis rather than the GHRH receptor. Critically, Ipamorelin shows high selectivity, it does not meaningfully elevate cortisol, prolactin, or ACTH at research-relevant doses. This selectivity makes it a preferred tool when investigators need clean GH data without adrenal confounders. A detailed comparison of Ipamorelin vs Tesamorelin highlights how these distinct receptor pathways produce overlapping yet distinct downstream effects.

CJC-1295 with DAC is a GHRH receptor agonist like Tesamorelin, but its Drug Affinity Complex (DAC) modification enables covalent albumin binding in circulation. This single structural change transforms the molecule's pharmacokinetic profile entirely, extending the effective half-life to approximately 6-8 days versus the roughly 30-minute half-life of unmodified GHRH analogs. The result is sustained, tonic GH and IGF-1 elevation rather than discrete pulses.

How Pulse Characteristics and IGF-1 Responses Differ Across Protocols

How Pulse Characteristics and IGF-1 Responses Differ Across Protocols

The pharmacokinetic differences above translate directly into measurable differences in study outcomes. The table below summarizes the key parameters researchers should account for when designing protocols.

Parameter Tesamorelin Ipamorelin CJC-1295 with DAC
Receptor target GHRH-R GHS-R1a GHRH-R
Half-life ~30 min ~2 hours 6-8 days
GH pulse shape Sharp, physiological Sharp, selective Broad, sustained
IGF-1 trajectory Moderate elevation Moderate elevation Prolonged elevation
Dosing frequency Daily Daily or BID Weekly

"The DAC modification does not simply extend duration, it fundamentally changes the nature of GH secretion from pulsatile to tonic, which has downstream consequences for IGF-1 kinetics and receptor sensitivity."

Tesamorelin produces sharp, physiologically patterned GH pulses when dosed daily. Its IGF-1 response is consistent and well-characterized, making it ideal for studies requiring predictable, repeatable GH stimulation. Researchers can explore Tesamorelin peptide benefits and Tesamorelin dosage per day considerations when planning acute or subchronic protocols.

Ipamorelin generates similarly sharp pulses but through the ghrelin axis. Because its mechanism is independent of GHRH-R, it can be combined with GHRH analogs for synergistic GH release, a common rationale behind combination blends. Dosing guidance for CJC-1295 Ipamorelin dosage protocols reflects this synergistic design logic.

CJC-1295 with DAC drives sustained IGF-1 elevation that persists across the dosing interval. Weekly dosing designs are both practical and sufficient, but researchers must account for the tonic GH environment when interpreting anabolic or metabolic endpoints. The prolonged exposure also raises considerations around somatostatin feedback that do not apply to short-acting analogs.

Choosing the Right Peptide or Combination for Your Research Design

Choosing the Right Peptide or Combination for Your Research Design

Choosing the Right Peptide or Combination for Your Research Design

Selecting among these three compounds, or combining them, depends on the specific research question.

For acute GH pulse studies: Tesamorelin or Ipamorelin are the better choices. Their short half-lives allow investigators to control timing precisely and measure discrete pulse amplitude and frequency.

For sustained IGF-1 elevation studies: CJC-1295 with DAC is the logical candidate. Its weekly dosing simplifies long-duration protocols and reduces injection frequency as a confounding variable.

For combination protocols: Pairing Ipamorelin (GHS-R1a) with a GHRH-R agonist (Tesamorelin or CJC-1295 with DAC) leverages dual-axis stimulation. Researchers planning such designs should consult an assay planning and sourcing checklist for CJC-1295 Ipamorelin before finalizing their protocol. Multi-peptide blends such as the Tesamorelin CJC-1295 Ipamorelin 12mg blend are increasingly used in research settings where dual-axis stimulation is the experimental goal.

Key protocol considerations include:

  • Sampling windows: Short-acting peptides require frequent sampling (every 15-30 minutes post-dose); CJC-1295 with DAC allows wider intervals.
  • IGF-1 measurement timing: Tonic GH from DAC formulations elevates baseline IGF-1 continuously; acute studies need pre-dose baselines reset between sessions.
  • Somatostatin feedback: Prolonged GH stimulation may upregulate somatostatin tone, potentially blunting peak responses in extended DAC studies.
  • Assay interference: Cortisol and prolactin co-measurements are more critical in protocols using non-selective secretagogues.

Conclusion

The distinctions among Tesamorelin, Ipamorelin, and CJC-1295 With DAC in shaping growth hormone study outcomes are not subtle, they are mechanistically fundamental. Tesamorelin offers physiological GHRH-R fidelity with acute pulse control. Ipamorelin delivers selective ghrelin-axis stimulation without adrenal noise. CJC-1295 with DAC redefines the exposure profile entirely through albumin binding, converting pulsatile release into sustained tonic elevation.

Actionable next steps for research teams in 2026:

  1. Define the primary endpoint first, acute pulse amplitude, sustained IGF-1 elevation, or dual-axis synergy, then select the compound that matches that endpoint mechanistically.
  2. Review CJC-1295 Ipamorelin cycle design principles to align dosing intervals with the chosen compound's half-life.
  3. Use a Tesamorelin dosage calculator when standardizing per-subject dosing in Tesamorelin-inclusive protocols.
  4. Document the pharmacokinetic rationale for compound selection in all study reports to improve cross-lab reproducibility.

Matching the right GHRH mimetic profile to the right research question is the single most impactful decision a lab can make before the first assay runs.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/tesa-ipamorelin-and-cjc-1295-with-dac-how-different-ghrh-mimetic-profiles.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-06 13:04:112026-08-06 13:04:11Tesamorelin, Ipamorelin, and CJC-1295 With DAC: How Different GHRH Mimetic Profiles Shape Growth Hormone Study Outcomes

Tag Archive for: igf-1 research

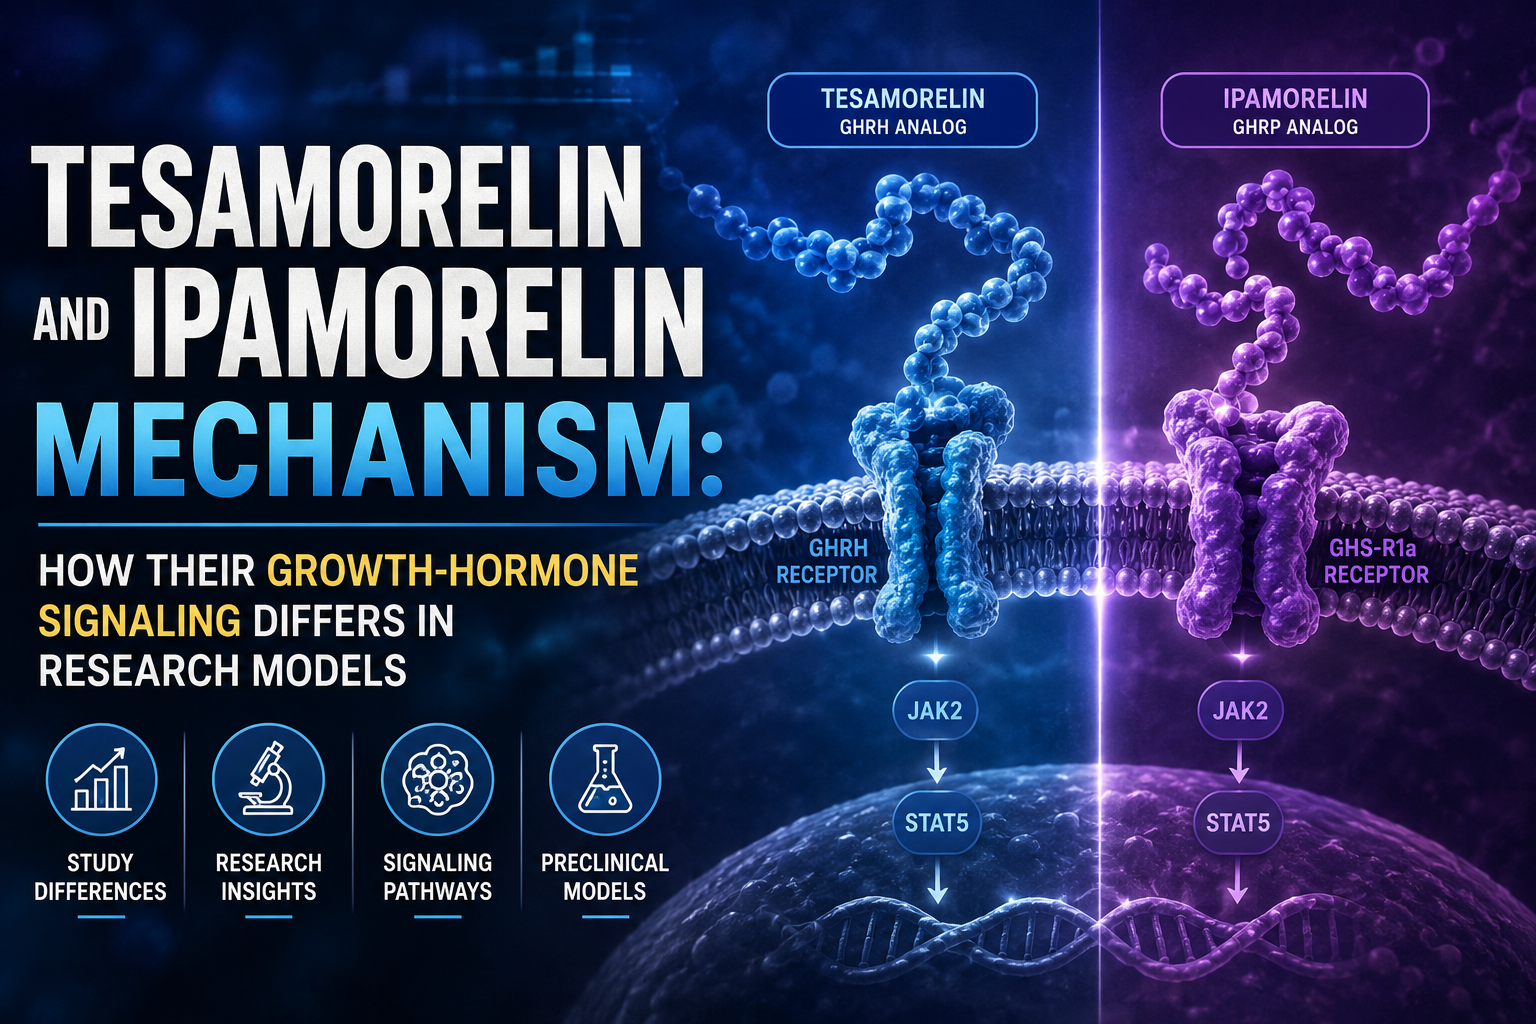
Tesamorelin and Ipamorelin Mechanism: How Their Growth-Hormone Signaling Differs in Research Models

Tesamorelin and Ipamorelin Mechanism: How Their Growth-Hormone Signaling Differs in Research Models

June 27, 2026/0 Comments/by Pure Tested

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay: 'Tesamorelin vs Ipamorelin: How Their GH Signaling Differs' in extra large 72pt white bold sans-serif font with dark semi-transparent overlay box, centered upper third. Background shows a dramatic close-up of a pituitary gland cross-section illustration merged with molecular receptor diagrams, deep navy blue and teal color palette, glowing cAMP and calcium signaling pathway nodes rendered in bright white and gold, editorial magazine cover quality, high contrast, scientific research aesthetic.","content":["Detailed landscape format (1536×1024) scientific diagram illustration showing two distinct receptor pathways side by side: left panel depicts GHRH receptor on a pituitary somatotroph cell with cAMP and PKA cascade arrows in cool blue tones, right panel shows GHS-R1a ghrelin receptor activating phospholipase C and intracellular calcium release in warm amber tones, labeled molecular nodes, clean white background with subtle lab texture, research infographic style, high contrast annotations, editorial quality","Landscape format (1536×1024) data visualization showing two overlapping GH pulse waveform graphs on a dark charcoal background: one smooth physiological pulsatile curve in electric blue representing Tesamorelin-driven GH release, one sharp clean spike in gold representing Ipamorelin-induced GH pulse, time axis labeled in hours, amplitude axis labeled in ng/mL, subtle grid lines, cortisol and prolactin flat reference lines in red dashes, preclinical research model aesthetic, clean scientific chart style, editorial quality","Landscape format (1536×1024) overhead view of a modern preclinical research laboratory bench showing two separate experimental setups: left side has molecular model of Tesamorelin peptide chain with trans-3-hexenoic acid modification highlighted in blue, right side shows Ipamorelin pentapeptide structure in gold, surrounded by pharmacokinetic half-life timeline bars, CT scan visceral fat reduction imagery in background, subtle teal and white lab aesthetic, research-grade editorial photography style, high contrast, scientific publication quality"}

Professional landscape hero image () with : "Tesamorelin and Ipamorelin Mechanism: How Their Growth-Hormone Signaling

Two peptides can both raise growth hormone levels yet work through entirely separate receptor systems — and that distinction matters enormously when designing preclinical studies. Understanding the Tesamorelin and Ipamorelin mechanism: how their growth-hormone signaling differs in research models is not simply academic. It determines which endpoints are valid, which biomarkers to track, and whether combining the two compounds makes mechanistic sense.


Key Takeaways

  • Tesamorelin activates the GHRH receptor via the cAMP/PKA pathway; ipamorelin activates the ghrelin receptor (GHS-R1a) via phospholipase C and intracellular calcium.
  • The two pathways are complementary, not redundant, making dual-pathway research designs scientifically justified.
  • Tesamorelin preserves physiological GH pulsatility; ipamorelin produces a selective, "clean" GH pulse without elevating cortisol or prolactin.
  • Half-life differences (25-40 minutes vs. approximately 2 hours) affect dosing interval choices in animal pharmacokinetic models.
  • IGF-1 elevation is a shared downstream endpoint, but the upstream signaling routes remain distinct.

Receptor-Level Differences That Define the Tesamorelin and Ipamorelin Mechanism

Receptor-Level Differences That Define the Tesamorelin and Ipamorelin Mechanism

At the receptor level, these two secretagogues operate on separate systems.

Tesamorelin is a synthetic analog of endogenous growth hormone-releasing hormone (GHRH). Its N-terminal modification with trans-3-hexenoic acid protects it from enzymatic degradation, extending its half-life to roughly 25-40 minutes. It binds selectively to the GHRH receptor (GHRHR) on anterior pituitary somatotrophs and activates the cAMP/PKA signaling cascade, which drives GH gene transcription and pulsatile secretion. This mechanism mirrors the body's own GHRH signaling, preserving the natural rhythm of GH release.

Ipamorelin takes a different route entirely. It is a selective agonist of the growth hormone secretagogue receptor type 1a (GHS-R1a) — the same receptor that endogenous ghrelin activates. Rather than cAMP, GHS-R1a engagement triggers phospholipase C (PLC) activation, leading to IP3-mediated calcium release from intracellular stores. This calcium surge is what drives GH secretion in ipamorelin-treated models.

Feature Tesamorelin Ipamorelin
Target Receptor GHRHR GHS-R1a (ghrelin receptor)
Signaling Cascade cAMP / PKA PLC / intracellular Ca2+
Half-Life ~25-40 minutes ~2 hours
GH Release Pattern Pulsatile, physiological Sharp, selective pulse
Cortisol / ACTH Effect Minimal Negligible

For researchers exploring ipamorelin muscle and fat research themes, this receptor distinction is foundational to interpreting results accurately.


GH Pulse Patterns and Downstream IGF-1 Endpoints in Research Models

GH Pulse Patterns and Downstream IGF-1 Endpoints in Research Models

The pattern of GH release produced by each compound is as important as the magnitude.

Tesamorelin's activation of GHRHR amplifies both basal and pulsatile GH secretion, closely replicating the endogenous GHRH-driven rhythm. This physiological pulsatility is considered advantageous in research models where mimicking natural GH dynamics is a priority. Studies examining tesa peptide benefits often highlight this feature as a key differentiator from synthetic GH administration.

Ipamorelin, by contrast, generates what researchers describe as a "clean" GH pulse. Its selectivity for GHS-R1a means it does not significantly elevate cortisol, ACTH, or prolactin — a profile that distinguishes it from earlier GH secretagogues like GHRP-6 or hexarelin. For models where hormonal specificity is critical, this selectivity reduces confounding variables. Detailed analysis of ipamorelin as a GH secretagogue underscores why this selectivity is valued in controlled research settings.

Downstream, both peptides elevate IGF-1, which serves as a practical shared endpoint. Tesamorelin's IGF-1 effects have been documented in Phase 3 clinical trials — including data from HIV-associated lipodystrophy studies showing measurable visceral adipose tissue (VAT) reduction via CT scan. Ipamorelin's IGF-1 elevation has been confirmed in preclinical models, though large-scale clinical quantification remains limited.

"The upstream receptor divergence between these two secretagogues does not prevent a shared downstream outcome — but it does mean the signaling routes, and therefore the research questions, are fundamentally different."


Preclinical Study Design: Applying the Tesamorelin and Ipamorelin Mechanism to Research Endpoints

Preclinical Study Design: Applying the Tesamorelin and Ipamorelin Mechanism to Research Endpoints

Understanding the Tesamorelin and Ipamorelin mechanism: how their growth-hormone signaling differs in research models has direct implications for study design.

Relevant preclinical endpoints include:

  • Serum GH pulse amplitude and frequency (assessed via serial blood sampling)
  • Plasma IGF-1 levels at defined intervals post-administration
  • Visceral fat mass via imaging or tissue dissection in rodent models
  • Cortisol and ACTH levels to confirm ipamorelin's hormonal selectivity
  • Muscle protein synthesis markers for anabolic pathway assessment

Because the two pathways are complementary — cAMP/PKA versus PLC/calcium — researchers have proposed dual-pathway designs that combine both compounds. The rationale is that simultaneous GHRHR and GHS-R1a activation may produce synergistic GH release exceeding what either compound achieves alone. Blended formulations explored in Tesamorelin, CJC-1295, and Ipamorelin combination research reflect this mechanistic logic.

Half-life differences also shape dosing interval decisions. Tesamorelin's shorter plasma stability (~25-40 minutes) suggests more frequent administration windows in acute models, while ipamorelin's approximately 2-hour half-life in animal pharmacokinetic studies supports less frequent dosing. Researchers reviewing CJC-1295 and ipamorelin combination dosing will find that pairing compounds with complementary half-lives is a common strategy to sustain GH elevation across a study window.

For broader context on metabolic peptide research, exploring metabolic modulation research lines provides useful comparative frameworks alongside GH secretagogue work.


Conclusion

The mechanistic contrast between tesa and ipamorelin is not a minor technical detail — it is the foundation of any rigorous research design involving these compounds. Tesamorelin drives GH release through GHRHR and cAMP/PKA signaling, preserving physiological pulsatility. Ipamorelin activates GHS-R1a and the PLC/calcium pathway, producing a selective GH pulse without hormonal side effects.

Actionable next steps for researchers:

  1. Define whether the study requires physiological GH pulsatility (favor tesa) or hormonal selectivity (favor ipamorelin) before choosing a compound.
  2. Use IGF-1 as a shared downstream biomarker while tracking pathway-specific markers (cAMP vs. intracellular calcium) to confirm receptor engagement.
  3. Consider dual-pathway designs when the research goal is maximal GH output, accounting for the complementary receptor systems.
  4. Align dosing intervals with each compound's half-life data from pharmacokinetic models to avoid under- or over-dosing in timed studies.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Tesamorelin-and-Ipamorelin-Mechanism-How-Their-Growth-Hormone-Signaling-Differs-in-Research-Models.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-27 13:04:472026-07-20 15:02:03Tesamorelin and Ipamorelin Mechanism: How Their Growth-Hormone Signaling Differs in Research Models
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top