Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: metabolic study design

Seroquel (Quetiapine) Confounding Metrics in Metabolic Studies: Isolating GLP-3 Retatrutide Weight Loss Signatures

Seroquel (Quetiapine) Confounding Metrics in Metabolic Studies: Isolating GLP-3 Retatrutide Weight Loss Signatures

October 29, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Seroquel (Quetiapine) Confounding Metrics' in crisp white sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge, two lines balanced in length, no character touches the edge. Background: split editorial composition showing a molecular receptor diagram on the left blending into a clinical metabolic data chart on the right, teal and deep blue color palette, medical research laboratory aesthetic, high-contrast editorial quality, magazine cover polish, bright studio lighting.","content":["Annotated mechanism-of-action diagram (1536×1024) showing quetiapine metabolic pathway disruption in a clinical research context. Three labeled panels side by side: Panel 1 labeled 'Weight Gain Pathway' showing H1/5-HT2C receptor blockade with callout lines to 'Hyperphagia', 'Insulin Resistance', 'Dyslipidemia'; Panel 2 labeled 'Metabolic Markers Affected' with callout labels 'Fasting Glucose', 'BMI Shift', 'Triglycerides', 'Leptin Dysregulation'; Panel 3 labeled 'Confounding Risk Level' with a simple graduated scale from Low to High. Teal-navy-white palette, clean white background, editorial medical-research style, sharp callout lines, labels 1-5 words each inside safe margins.","Split-screen editorial infographic (1536×1024) comparing GLP-3 retatrutide weight-loss signature isolation. Left half labeled 'With Quetiapine Confounder' showing a cluttered metabolic signal graph with overlapping lines, annotations 'Masked Fat Loss', 'Inflated Baseline BMI', 'Hyperphagic Offset'; right half labeled 'Controlled Study Design' showing a clean descending weight-loss curve with callouts 'True Fat Mass Reduction', 'Lean Mass Preserved', 'Triple Agonist Signal Isolated'. Bright clinical white background, warm amber vs cool teal color contrast between panels, bold dividing line center, medical data-visualization aesthetic, editorial quality.","Numbered step-by-step process flow diagram (1536×1024) for designing metabolic studies that isolate retatrutide efficacy from antipsychotic confounders. Five horizontal steps with connecting arrows: Step 1 'Screen for Quetiapine Use' with sub-label 'Dose and Duration Log'; Step 2 'Stratify by Antipsychotic Load' with sub-label 'Low vs High Exposure Groups'; Step 3 'Establish Metabolic Baseline' with sub-label 'Glucose, Lipids, BMI, MASLD Score'; Step 4 'Apply Statistical Controls' with sub-label 'Covariate Adjustment Models'; Step 5 'Isolate GLP-3 Signature' with sub-label 'Fat Mass vs Lean Mass Delta'. Deep navy background, teal accent arrows, white label boxes, bold step numbers in amber circles, editorial clinical research aesthetic, sharp and legible."]

Seroquel (Quetiapine) Confounding Metrics in Metabolic Studies: Isolating GLP-3 Retatrutide Weight Loss Signatures

Roughly one in five patients prescribed quetiapine for off-label conditions such as insomnia or anxiety gains more than 7% of their baseline body weight within the first year of treatment. When those same patients enter a retatrutide clinical trial, that pre-existing metabolic burden does not disappear, it hides inside the data. Addressing Seroquel (Quetiapine) confounding metrics in metabolic studies: isolating GLP-3 retatrutide weight loss signatures is therefore not a statistical nicety but a research imperative if clinicians are to trust what they see in the weight-loss curves.

Key Takeaways

  • Quetiapine causes dose-dependent weight gain, insulin resistance, and dyslipidemia that directly contaminate metabolic outcome data.
  • Retatrutide, a GLP-1/GIP/glucagon triple agonist, produces a distinct fat-preferential weight-loss signature that can be masked by antipsychotic-induced hyperphagia.
  • Failure to screen and stratify for quetiapine use inflates baseline BMI and distorts the apparent magnitude of GLP-3 efficacy.
  • Children and adolescents are disproportionately vulnerable to quetiapine metabolic side effects, making pediatric subgroup analysis especially error-prone.
  • Rigorous covariate adjustment and stratified randomization are the two highest-yield corrective strategies.

How Quetiapine Disrupts Metabolic Baselines

Quetiapine metabolic pathway disruption diagram with callout labels

Quetiapine's metabolic profile is driven by its antagonism of histamine H1 receptors and serotonin 5-HT2C receptors. Both of these receptor interactions promote appetite dysregulation, reduce satiety signaling, and encourage fat accumulation, particularly visceral fat. The result is a distinct pattern of antipsychotic-induced metabolic dysfunction that includes:

  • Weight gain: Averaging 2-5 kg in short-term studies; substantially more with chronic use.
  • Insulin resistance: Elevated fasting glucose and HOMA-IR scores, independent of weight change.
  • Dyslipidemia: Elevated triglycerides and reduced HDL cholesterol.
  • Leptin dysregulation: Altered adipokine signaling that obscures true energy balance.

Prospective cohort data confirm that these effects are dose-dependent. Patients on higher doses show faster and more pronounced shifts across every metabolic marker compared to those on low-dose regimens. Off-label use at lower doses does not confer immunity, even sub-therapeutic doses used for sleep produce measurable glucose and lipid changes over months.

Pediatric populations deserve special attention here. Children and adolescents demonstrate heightened vulnerability to quetiapine-induced metabolic shifts, with greater relative weight gain per milligram of exposure than adults. Any metabolic study that includes younger participants without stratifying for antipsychotic use is at particular risk of biased endpoints.

Key insight: A participant entering a retatrutide trial with two years of quetiapine exposure does not share the same metabolic starting point as a drug-naive control, even if their baseline BMI appears identical on paper.


The Retatrutide Weight-Loss Signature and Why It Is Vulnerable to Noise

Retatrutide weight-loss signal isolated from quetiapine confounding data

Retatrutide is a triple agonist acting at GLP-1, GIP, and glucagon receptors simultaneously. This tri-receptor mechanism creates a weight-loss signature that is both larger in magnitude and different in character from dual or single incretin agents. To understand what makes isolating that signature so difficult, and so important, it helps to know what the signature actually looks like.

Phase 2 trial data show retatrutide producing mean weight reductions in the range of 17-24% of body weight over approximately 48 weeks, placing it among the strongest peptides for weight loss currently in clinical development. Body-composition substudies reveal that the majority of lost mass is adipose tissue, with a relatively preserved lean mass fraction, a fat-preferential signature that is pharmacologically meaningful and clinically distinguishable.

Retatrutide also shows promising results in metabolic dysfunction-associated steatotic liver disease (MASLD), reducing hepatic fat fraction alongside systemic adiposity. This multi-organ benefit makes precise attribution of metabolic changes especially important: researchers need to know whether liver improvements stem from the drug's direct action or from generalized weight loss that any intervention might have produced.

The problem is that quetiapine's pro-hyperphagic effects work in exactly the opposite direction. When a patient simultaneously experiences antipsychotic-driven appetite increases and GLP-3-driven appetite suppression, the net weight-loss signal is attenuated. The GLP-3 Reta mechanism is not negated, but its apparent magnitude shrinks. Researchers who do not account for this interaction may conclude that retatrutide underperformed when in reality the drug achieved its expected pharmacological effect against a metabolic headwind.

Three mechanisms of signal distortion:

  1. Hyperphagic offset, antipsychotic-driven caloric intake partially cancels appetite suppression.
  2. Baseline inflation, elevated pre-trial BMI and glucose shift the apparent responder rate.
  3. Regression-to-mean artifact, patients with quetiapine-elevated baselines show large apparent drops early if the antipsychotic dose is also adjusted during the trial.

Isolating the GLP-3 Signal: Study Design and Statistical Controls

Step-by-step study design flow for isolating retatrutide metabolic signal

Addressing Seroquel (Quetiapine) confounding metrics in metabolic studies: isolating GLP-3 retatrutide weight loss signatures requires intervention at three levels: enrollment screening, randomization strategy, and post-hoc statistical adjustment.

Enrollment and screening protocols

The first corrective step is comprehensive antipsychotic exposure logging at screening. This means recording not just current quetiapine use but historical dose, cumulative duration, and any dose changes in the 90 days before enrollment. Researchers sourcing Reta peptide for preclinical work should apply the same principle: animal models with prior antipsychotic exposure require separate analysis tracks.

Stratified randomization

Participants should be stratified by quetiapine exposure status (none, low-dose, high-dose, discontinued) before randomization. This prevents accidental clustering of antipsychotic users in one arm and ensures that any residual confounding is balanced across groups.

Covariate adjustment models

Post-hoc, quetiapine dose and duration should enter the regression model as continuous covariates alongside standard metabolic variables. Mixed-effects models that account for time-varying quetiapine dose changes are especially valuable in longer trials where psychiatric medication management may shift.

Subgroup-specific benchmarks

Quantitative expectations for retatrutide weight loss differ meaningfully between antipsychotic-naive participants and those carrying metabolic burden from quetiapine. Establishing drug-class-specific response benchmarks, rather than applying a single trial-wide threshold, improves sensitivity for detecting true responders in each subgroup.

Researchers and clinicians sourcing Reta 20mg or GLP-3 Reta 30mg formulations for investigational use should document all concomitant medications with metabolic implications. For broader context on available formulations, the Glp3 Reta Cag 10mg option may also be relevant depending on dosing protocol.

Practical checklist for metabolic study design:

  • Screen all participants for current and recent antipsychotic use
  • Record quetiapine dose, duration, and formulation (immediate vs. extended-release)
  • Stratify randomization by antipsychotic exposure category
  • Include quetiapine dose as a time-varying covariate in primary analysis
  • Pre-specify subgroup analyses for quetiapine-exposed vs. naive participants
  • Apply drug-class-specific response benchmarks when interpreting efficacy

Conclusion

The intersection of Seroquel (Quetiapine) confounding metrics in metabolic studies: isolating GLP-3 retatrutide weight loss signatures represents one of the most practically important, and most overlooked, design challenges in modern obesity pharmacology. Quetiapine's well-documented capacity to drive weight gain, dysregulate glucose metabolism, and blunt satiety signaling creates a systematic bias that can shrink or distort the apparent efficacy of one of the most potent incretin agents in development.

Actionable next steps for researchers and clinicians:

  • Implement mandatory antipsychotic exposure screening in all retatrutide and incretin-class trial protocols starting in 2026.
  • Adopt stratified randomization as a standard rather than optional design element.
  • Pre-register subgroup analyses for antipsychotic-exposed participants so results are not dismissed as post-hoc.
  • Collaborate with psychiatric co-investigators to capture real-world quetiapine dose fluctuations that occur during long trials.
  • Apply drug-specific metabolic benchmarks when counseling patients currently on quetiapine who are beginning GLP-3 therapy, so that attenuated early response is correctly interpreted rather than misread as treatment failure.

The weight-loss signature that retatrutide produces is pharmacologically robust. Protecting its visibility in data, by rigorously controlling for antipsychotic-induced metabolic dysfunction, is the research community's responsibility.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/seroquel-quetiapine-confounding-metrics-in-metabolic-studies-isolating-glp-3-ret.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-29 13:19:102026-10-29 13:19:10Seroquel (Quetiapine) Confounding Metrics in Metabolic Studies: Isolating GLP-3 Retatrutide Weight Loss Signatures
Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies

Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies

October 6, 2026/0 Comments/in Uncategorized/by

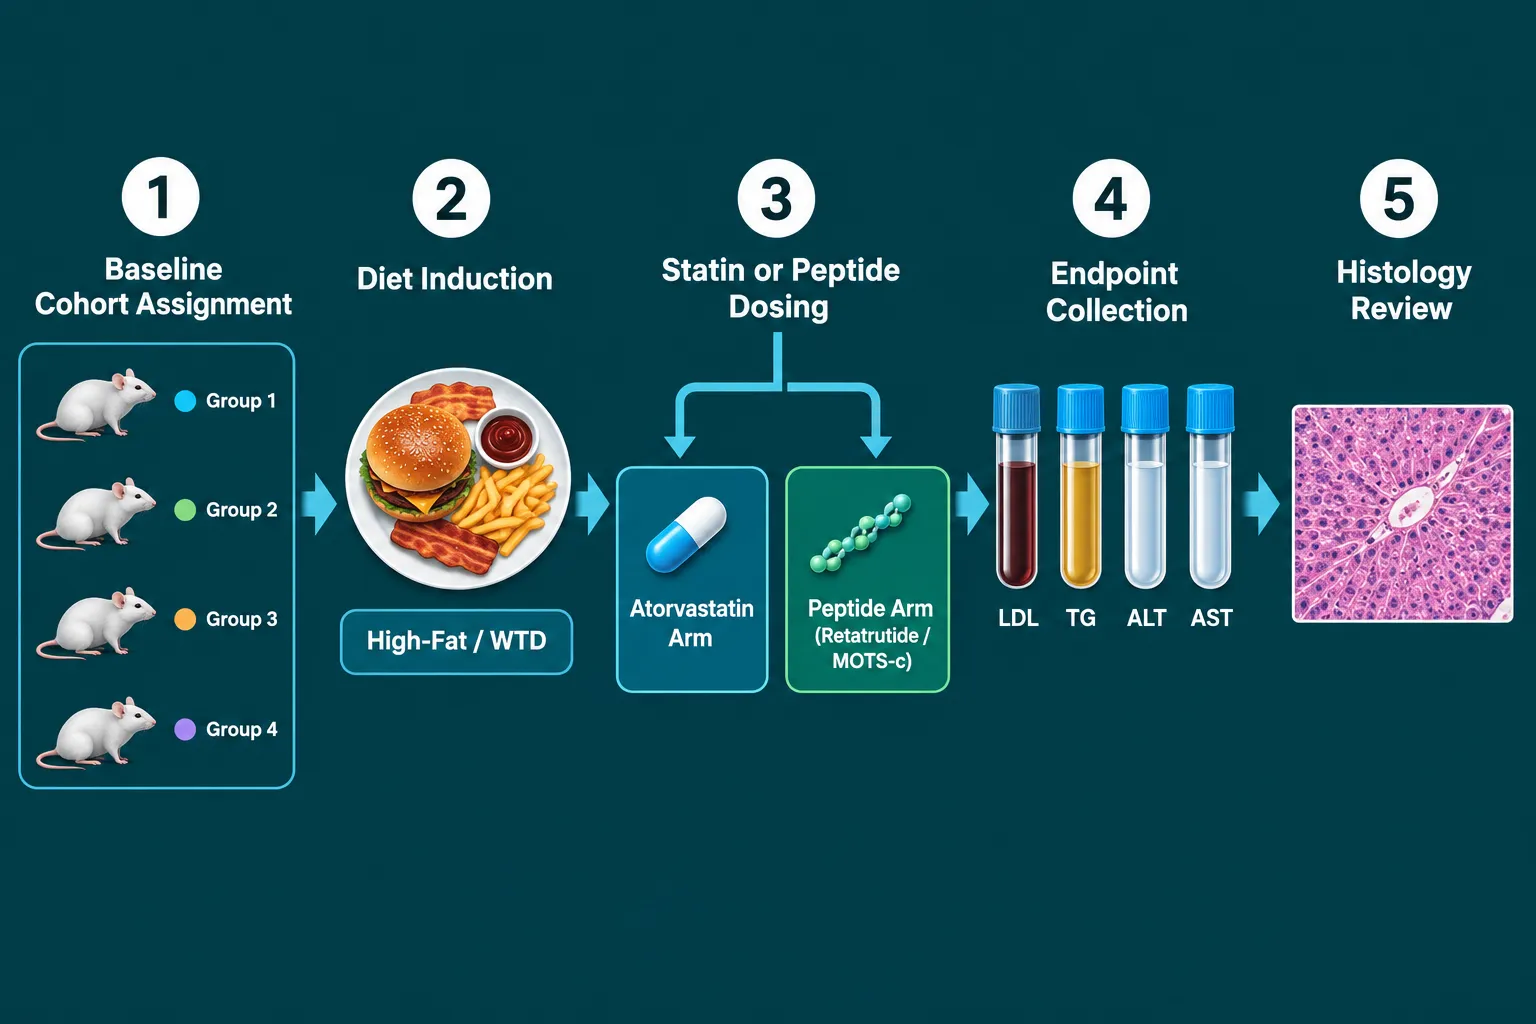
Cardiovascular disease remains the leading cause of death worldwide, yet fewer than half of high-risk research subjects in preclinical metabolic models reach target lipid endpoints without a standardized control framework. Designing rigorous control groups is where most metabolic studies succeed or fail, and the intersection of Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies sits at the center of that challenge. As novel peptides such as retatrutide, MOTS-c, and 5-amino-1MQ enter metabolic research pipelines, pairing them against a well-characterized statin benchmark like atorvastatin is no longer optional, it is methodologically essential.

Key Takeaways

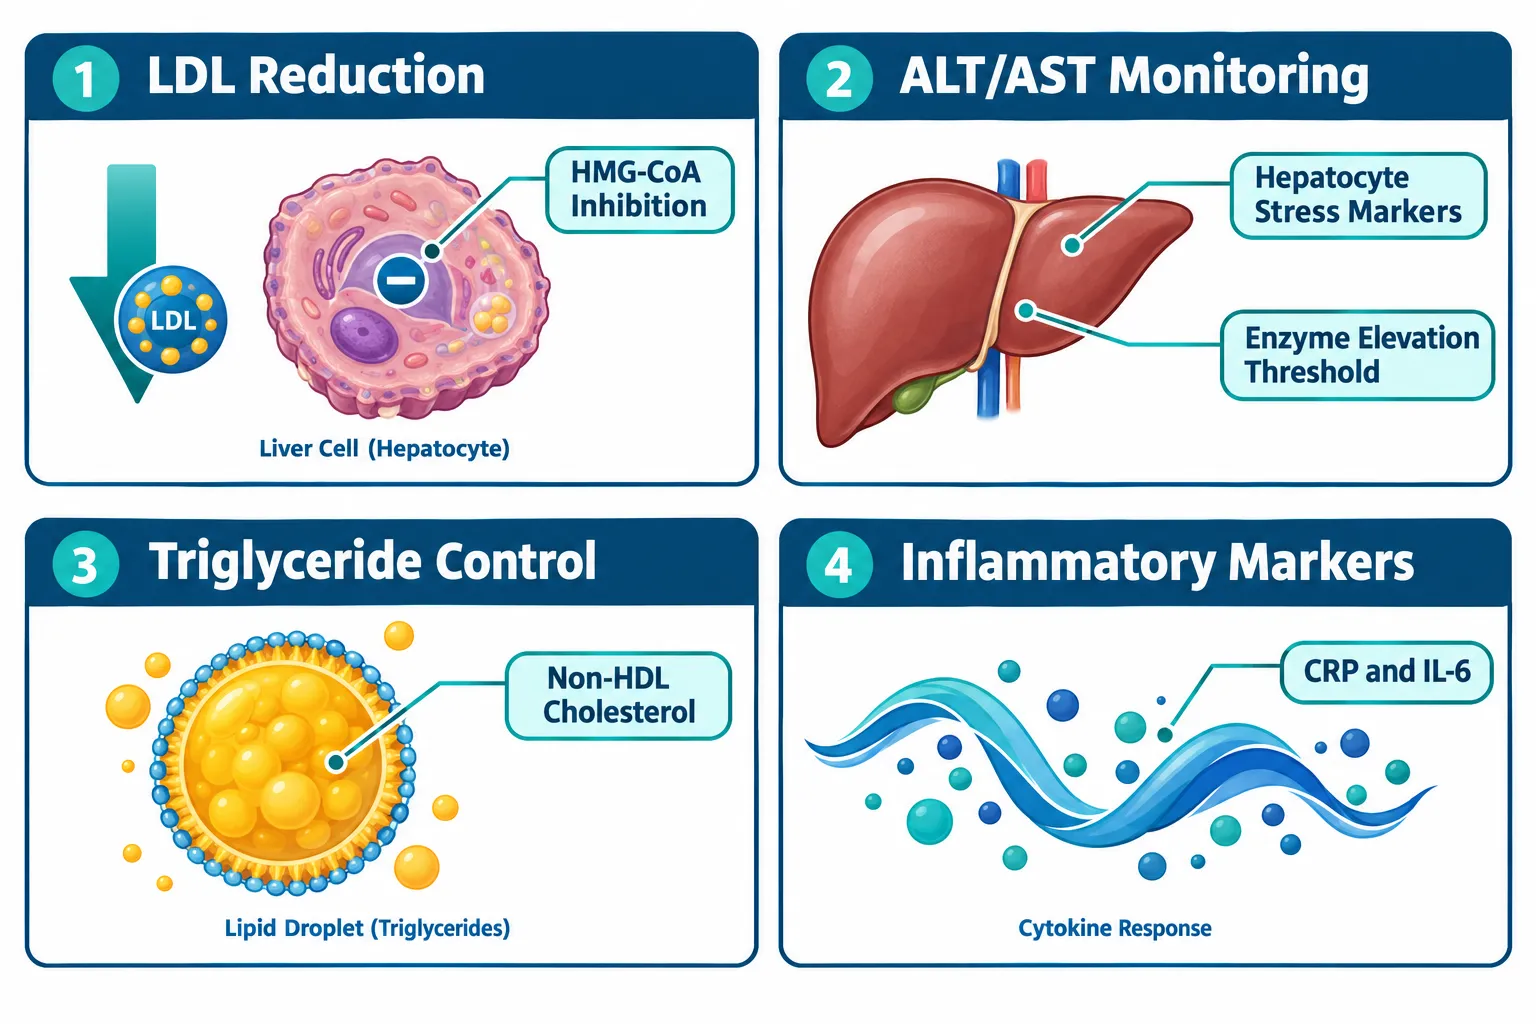
  • Atorvastatin reliably lowers LDL, triglycerides, and non-HDL cholesterol, making it the gold-standard lipid control comparator in metabolic studies.
  • Liver safety endpoints, particularly ALT, AST, and histological steatosis scores, must be tracked in every atorvastatin-containing control arm.
  • Peptide arms (retatrutide, MOTS-c, 5-amino-1MQ) require a statin-exposed control group to isolate peptide-specific metabolic contributions.
  • Western-type diet (WTD) models with and without atorvastatin remain the canonical structure for NAFLD and hyperlipidemia research designs.
  • Multi-arm study designs that combine diet, statin exposure, and peptide co-therapy now represent the evolving standard in 2026 metabolic research.

Why Atorvastatin Anchors Lipid and Liver-Control Group Design

Why Atorvastatin Anchors Lipid and Liver-Control Group Design

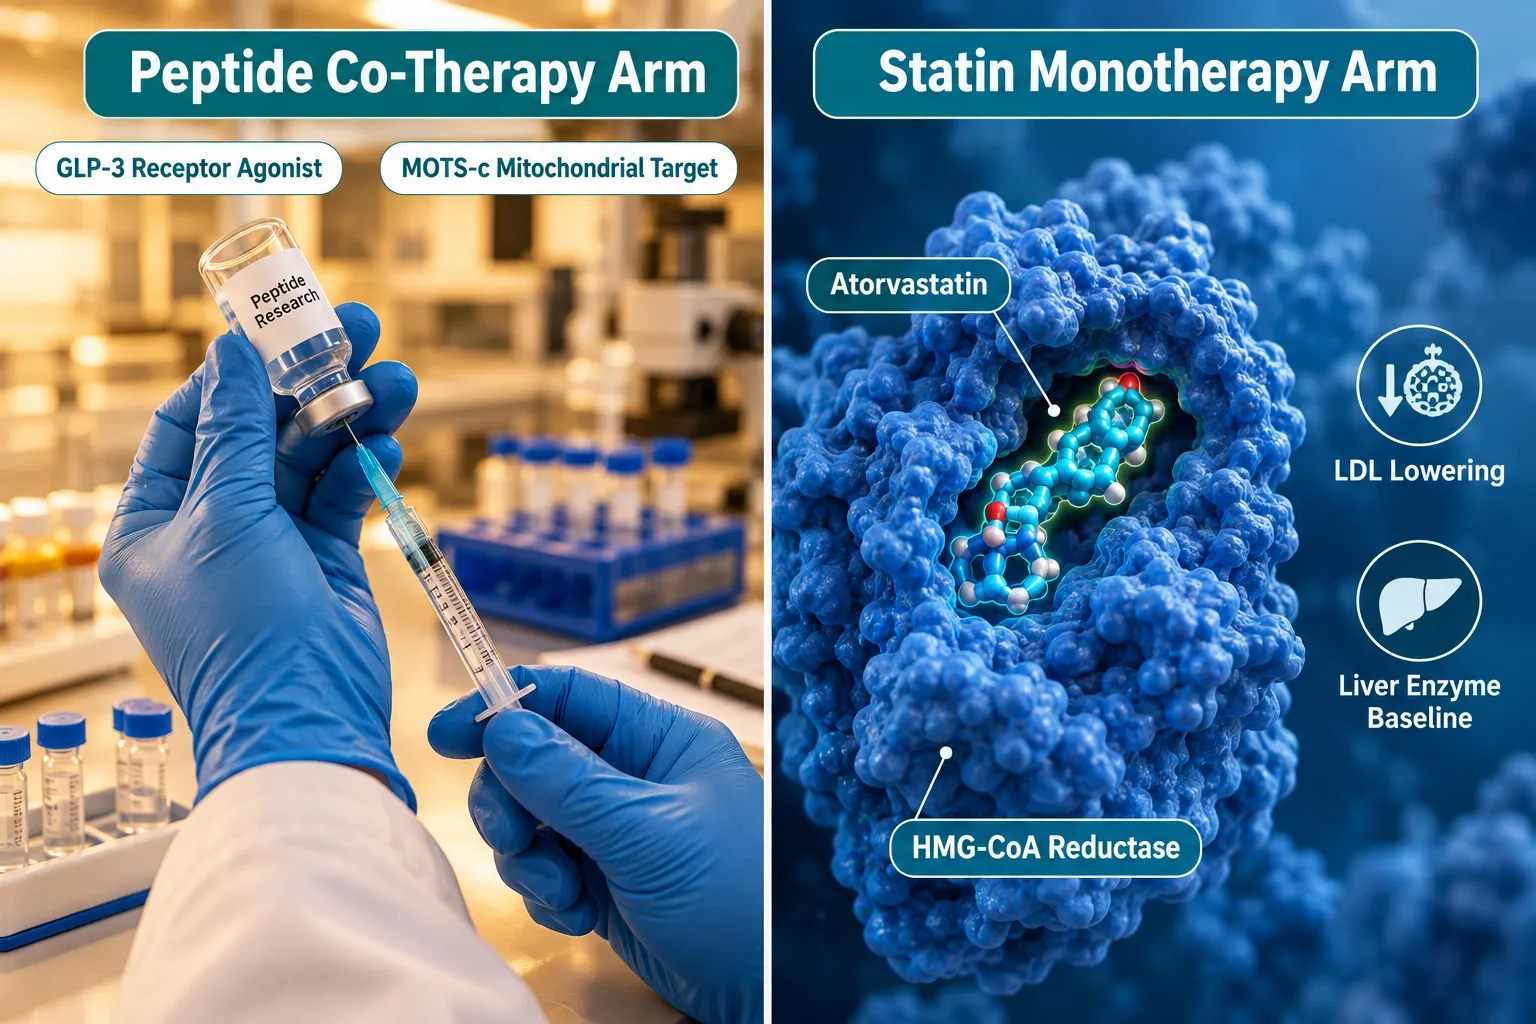
Atorvastatin is a high-intensity HMG-CoA reductase inhibitor with a well-mapped pharmacological profile. In metabolic research, that predictability is an asset. When a study introduces a novel peptide, researchers need a control arm whose lipid and liver effects are already understood, atorvastatin provides exactly that anchor.

Key lipid biomarkers affected by atorvastatin exposure include:

  • LDL cholesterol, typically reduced 40-55% at standard research doses
  • Triglycerides, modestly lowered, relevant in high-fat diet models
  • Non-HDL cholesterol, a composite marker that captures atherogenic particle burden
  • HDL cholesterol, marginally elevated, though not the primary endpoint

On the liver side, atorvastatin is metabolized extensively through CYP3A4 hepatic pathways. This makes ALT (alanine aminotransferase) and AST (aspartate aminotransferase) critical safety and efficacy readouts in every control arm. Current evidence from 2026 confirms that atorvastatin is safe even in subjects with advanced chronic liver disease, though transient enzyme elevations can occur and must be tracked systematically.

"A control group without liver enzyme monitoring is not a control group, it is an incomplete experiment."

For NAFLD and NASH models, atorvastatin also reduces hepatic steatosis scores and portal pressure markers. This means the "normal + atorvastatin" control arm carries meaningful liver biology, not just a lipid signal.


Structuring Multi-Arm Designs for Retatrutide, MOTS-c, and 5-Amino-1MQ Studies

Structuring Multi-Arm Designs for Retatrutide, MOTS-c, and 5-Amino-1MQ Studies

When Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies are combined in a multi-arm preclinical model, the architecture of the study determines what conclusions are actually possible. A poorly structured design cannot separate statin effects from peptide effects, and that ambiguity destroys interpretive value.

Recommended Multi-Arm Framework

Arm Diet Statin Peptide Primary Readouts
Vehicle Control Standard chow None None Baseline LDL, ALT, AST
Lipid Control WTD Atorvastatin None LDL, TG, non-HDL, ALT
Peptide Arm A WTD None Retatrutide GLP receptor activity, lipids
Peptide Arm B WTD None MOTS-c Mitochondrial markers, AST
Combination Arm WTD Atorvastatin Retatrutide or MOTS-c All lipid + liver endpoints

Retatrutide targets GLP-1, GIP, and glucagon receptors simultaneously, producing meaningful reductions in body weight and triglycerides. For researchers exploring this compound, the Buy Retatrutide Peptide resource provides relevant formulation context. When placed against an atorvastatin lipid-control arm, the incremental triglyceride and non-HDL reduction attributable to retatrutide becomes statistically isolatable.

MOTS-c operates through mitochondrial AMPK activation, influencing glucose metabolism and fatty acid oxidation. Its liver effects, particularly on hepatic lipid accumulation, overlap with atorvastatin's steatosis-reducing properties. Researchers sourcing this compound can reference the Buy MOTS-c Peptide page for purity and dosing specifications. The MOTS-c Peptide Dosage Calculator is also a practical tool for designing consistent dosing protocols.

5-amino-1MQ inhibits NNMT (nicotinamide N-methyltransferase), shifting cellular metabolism toward fat oxidation. Its inflammatory marker profile, including CRP and IL-6, makes it particularly important to track alongside ALT and AST in the atorvastatin control arm, since both compounds affect hepatic inflammatory tone.

For broader context on how these peptides compare mechanistically to small-molecule drugs, the article on Polypeptide Peptides in Cardiometabolic Models provides a strong conceptual foundation.


Liver-Centric Endpoints and Inflammatory Marker Integration

Liver-Centric Endpoints and Inflammatory Marker Integration

The most common failure in Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies is treating liver safety as secondary. In 2026, the evidence base has shifted firmly: liver endpoints are co-primary, not supplementary.

Liver-centric endpoints to include in every control arm:

  1. ALT and AST, tracked at baseline, mid-study, and endpoint; atorvastatin can cause transient elevations that must be distinguished from peptide-induced changes
  2. Hepatic steatosis score, histological grading from liver biopsy or MRI-based fat fraction
  3. Portal pressure markers, relevant in advanced NAFLD/NASH models
  4. Liver-to-body weight ratio, a rapid structural readout in rodent models

Inflammatory markers add a second interpretive layer. CRP, IL-6, and TNF-alpha are all modulated by atorvastatin through pleiotropic anti-inflammatory mechanisms. When a peptide like MOTS-c or GLP-3 peptide also reduces inflammatory load, the atorvastatin control arm provides the benchmark against which that reduction is measured.

Combination therapy designs, such as "phosphatidylcholine (PPC) alone" versus "PPC + atorvastatin", demonstrate how isolating statin-specific contributions requires a clean single-agent control. The same logic applies when adding SS-31 peptides to a metabolic model: the mitochondria-targeted antioxidant effects of SS-31 must be separated from atorvastatin's lipid-lowering signal through deliberate arm structure.

Monitoring schedule best practices:

  • Collect lipid panels at weeks 0, 4, 8, and 12 minimum
  • Run liver enzyme panels at the same intervals
  • Reserve histology for endpoint only (terminal in rodent models)
  • Include fasting insulin and HOMA-IR as metabolic co-endpoints

Conclusion

Designing rigorous control groups for metabolic peptide research is not a procedural formality, it is the scientific foundation on which every meaningful comparison rests. Atorvastatin's well-characterized effects on LDL, triglycerides, non-HDL cholesterol, ALT, and AST make it the most defensible lipid and liver-control comparator available for studies involving retatrutide, MOTS-c, or 5-amino-1MQ.

Actionable next steps for researchers in 2026:

  • Build a minimum five-arm design that separates vehicle, statin, peptide, and combination conditions
  • Pre-specify all liver enzyme thresholds as stopping rules and safety endpoints
  • Use Western-type diet induction as the metabolic stressor to activate both lipid and hepatic pathways
  • Align inflammatory marker panels (CRP, IL-6) with lipid and liver readouts for mechanistic depth
  • Consult formulation-specific resources for peptide purity verification before dosing begins

A well-structured control group does not slow research down, it makes the data worth publishing.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/atorvastatin-and-research-peptides-designing-lipid-and-liver-control-groups-for.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-06 13:10:132026-10-06 13:10:13Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies
Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design

Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design

September 13, 2026/0 Comments/in Uncategorized/by

Participants in the TRIUMPH-1 Phase 3 trial lost an average of 28 to 30 percent of their body weight over 80 to 104 weeks, a figure that would have seemed implausible in obesity pharmacology just five years ago. That single data point from retatrutide's pivotal program captures why Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design has become one of the most closely watched conversations in metabolic medicine. The compound, informally called "GLP-3" because it adds glucagon receptor agonism on top of the GLP-1 and GIP dual-agonism already seen in tirzepatide, is forcing researchers to rethink how trials are designed, how endpoints are selected, and how combination strategies should be structured.

Key Takeaways

  • Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, earning the informal label "GLP-3" in research circles.
  • Phase 3 TRIUMPH trials are reporting weight loss figures of 28 to 30 percent, well above prior incretin benchmarks.
  • TRANSCEND-T2D-1 data show roughly 17 percent weight loss alongside strong glycemic control at 40 weeks.
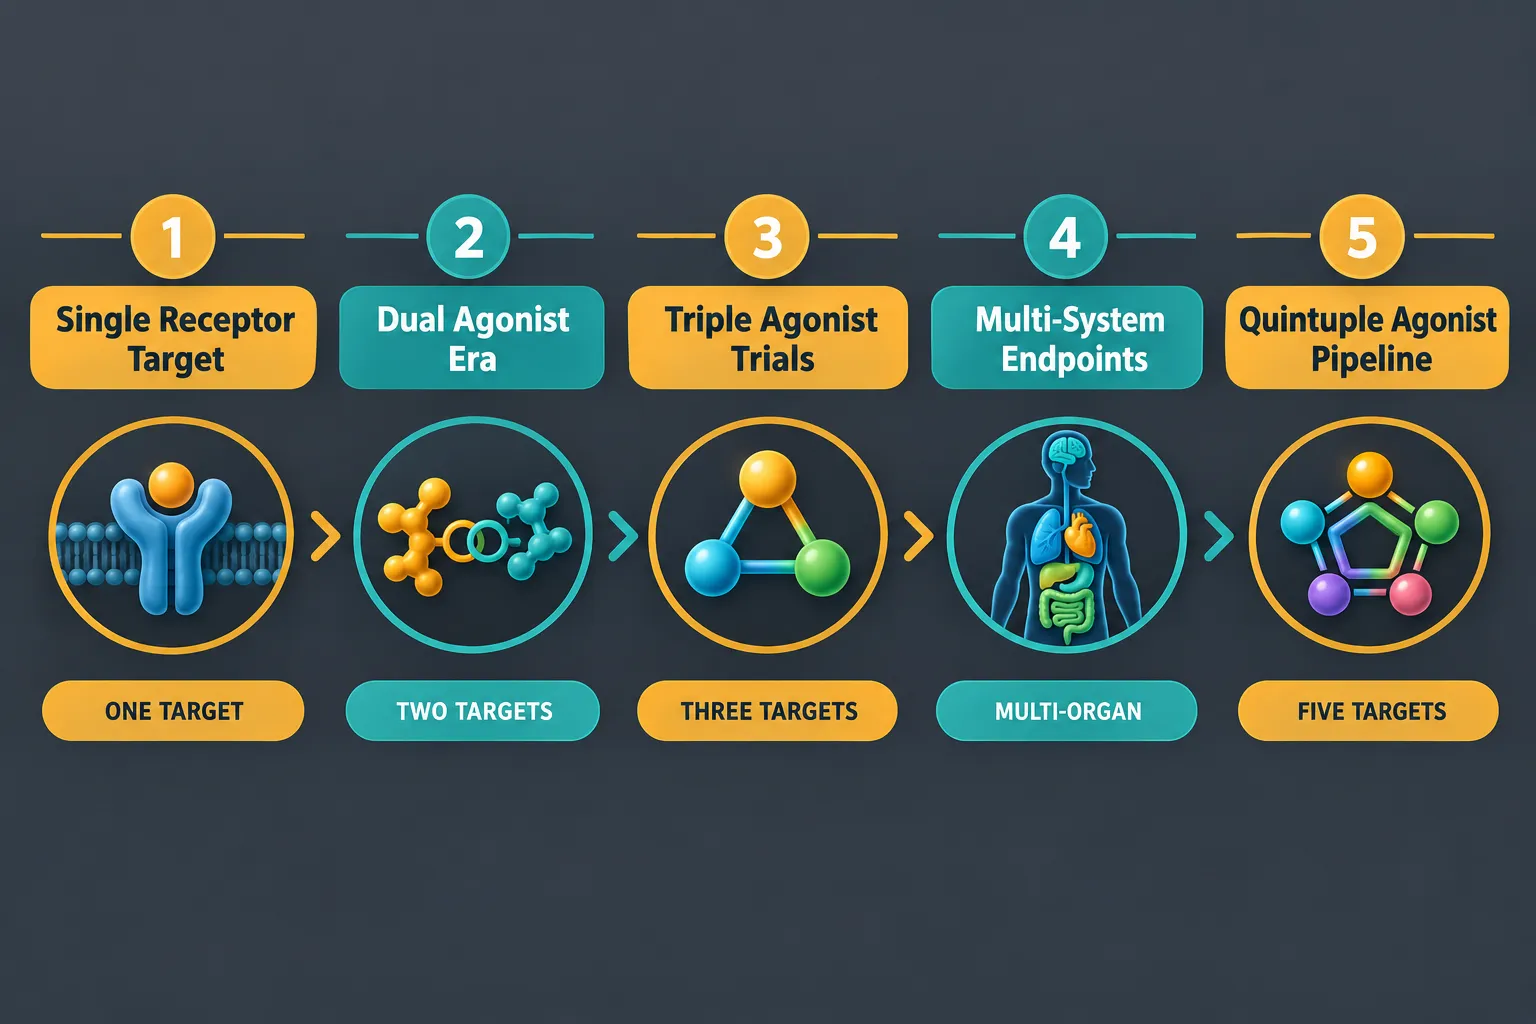
  • Triple agonist results are pushing trial designers toward longer durations, multi-system endpoints, and broader inclusion criteria.
  • A broader pipeline, including Novo Nordisk's UBT251 and early quintuple agonist candidates, is accelerating the shift from single-target to multi-target metabolic drug development.

What "GLP-3" Actually Means: The Triple Receptor Mechanism

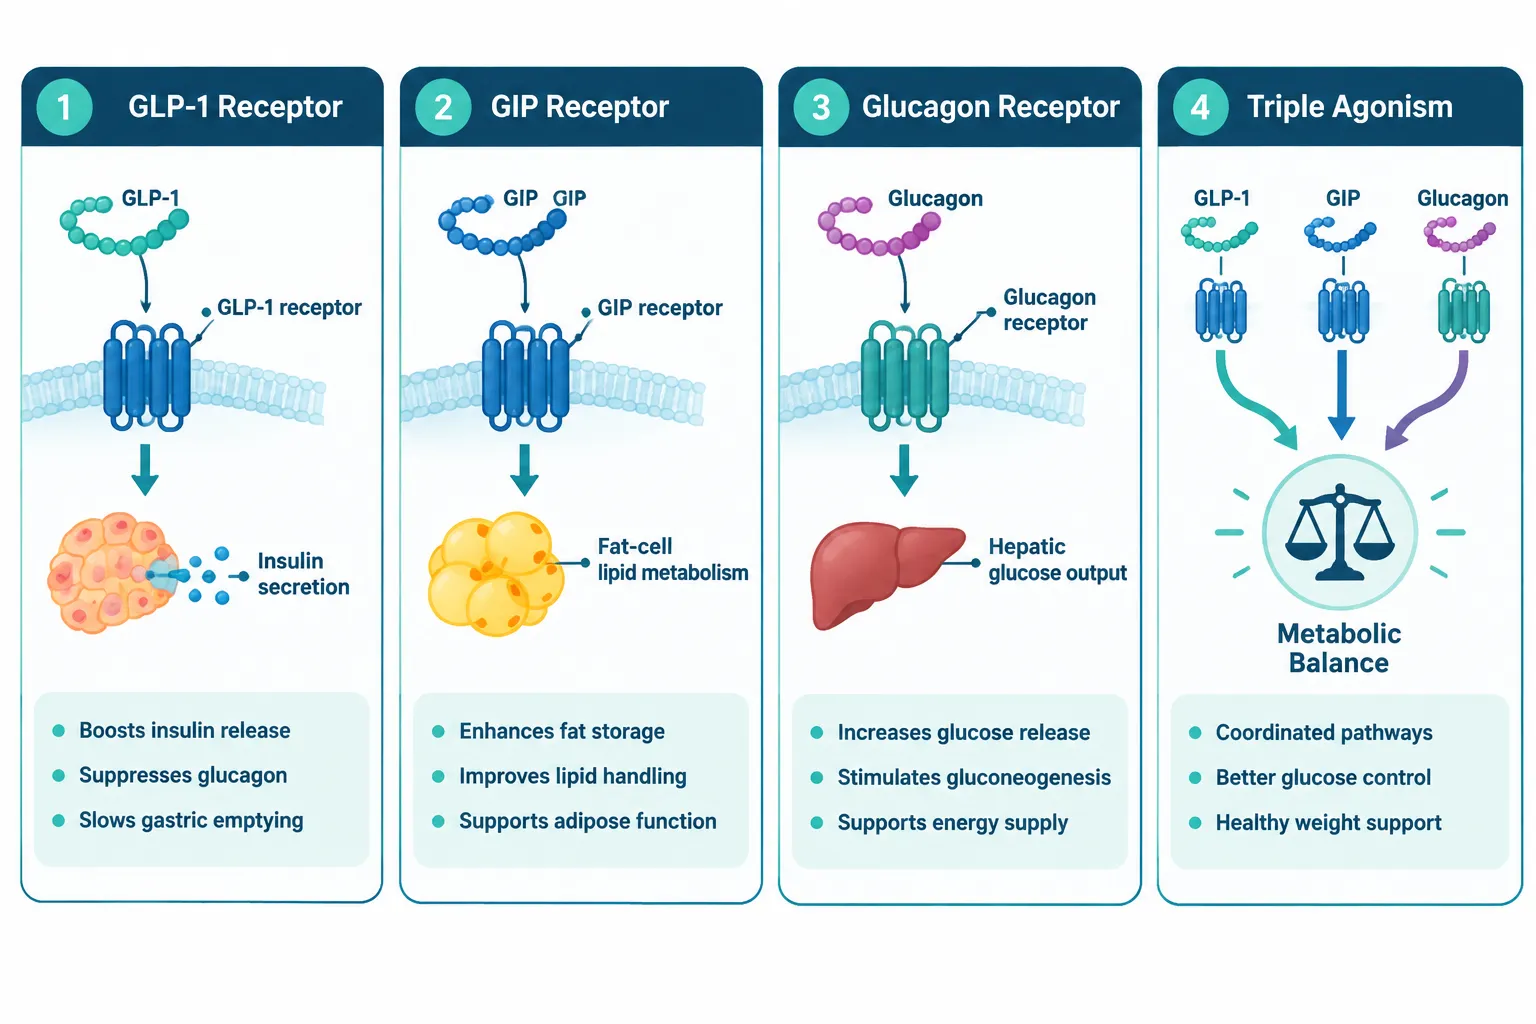
The nickname "GLP-3" is not an official receptor designation but a shorthand that reflects retatrutide's three-pronged mechanism. By co-activating the glucagon-like peptide-1 receptor, the glucose-dependent insulinotropic polypeptide receptor, and the glucagon receptor, the molecule targets energy intake, insulin sensitivity, and hepatic glucose output simultaneously.

What "GLP-3" Actually Means: The Triple Receptor Mechanism

This layered approach distinguishes retatrutide from earlier incretin therapies. GLP-1 agonism suppresses appetite and slows gastric emptying. GIP agonism enhances insulin secretion and may improve fat metabolism. Glucagon receptor agonism drives energy expenditure and accelerates hepatic fat clearance, a feature with direct implications for metabolic-associated steatotic liver disease (MASLD) research.

For researchers exploring the broader landscape of polypeptide peptides in cardiometabolic models, the triple agonist profile represents a meaningful departure from classic small-molecule drugs. Those interested in sourcing reference compounds for preclinical work can review options such as the GLP-3R 30mg Peptide GA8 or the GLP-3 Reta 30mg to understand the structural variants in active use.

Key receptor targets at a glance:

Receptor Primary Metabolic Effect
GLP-1R Appetite suppression, insulin secretion
GIPR Enhanced insulin response, fat metabolism
Glucagon R Energy expenditure, hepatic fat clearance

How Triple Agonist Trial Data Is Changing Metabolic Study Design

The TRIUMPH program illustrates how Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design is influencing the entire field, not just the Eli Lilly pipeline. TRIUMPH-1 enrolled adults with obesity but without type 2 diabetes and ran to 80 to 104 weeks, significantly longer than most prior Phase 3 obesity trials. TRIUMPH-2 and TRIUMPH-3 extend the complexity further by enrolling participants with obesity plus serious complications, including type 2 diabetes and established cardiovascular disease.

How Triple Agonist Trial Data Is Changing Metabolic Study Design

The TRANSCEND-T2D-1 diabetes-focused trial adds another layer. At 40 weeks, participants showed approximately 17 percent weight loss alongside robust glycemic control, outcomes that are prompting endocrinology researchers to reconsider whether weight loss should be a primary rather than secondary endpoint in diabetes trials.

"The shift is not just about better drugs, it is about better questions. Triple agonist data demands that trials ask what happens to the liver, the heart, and the vasculature simultaneously."

Several design changes are now appearing across the metabolic research landscape:

  • Longer trial durations, 80 to 104 weeks is becoming a new baseline for obesity studies.
  • Broader inclusion criteria, cardiovascular and hepatic comorbidities are now inclusion factors rather than exclusion factors.
  • Multi-system primary endpoints, weight, HbA1c, liver fat fraction, and cardiovascular biomarkers are being co-primary or key secondary endpoints.
  • MASLD-specific substudies, given glucagon receptor involvement in hepatic fat clearance, liver imaging endpoints are increasingly standard.

Researchers tracking retatrutide clinical trials and retatrutide endpoints will find that these design shifts are already visible in newly registered protocols. The visceral fat research tag aggregates complementary data on adipose tissue outcomes that are increasingly central to these expanded endpoint frameworks.

Safety, the Broader Pipeline, and What Comes Next

Retatrutide's tolerability profile follows the incretin class pattern: nausea, vomiting, and gastrointestinal discomfort are the most common adverse events, with rates generally manageable through dose escalation protocols. The longer trial durations in TRIUMPH-2 and TRIUMPH-3 are generating richer safety datasets than earlier Phase 2 work, including the foundational New England Journal of Medicine Phase 2 publication that first established the compound's potency benchmark.

Safety, the Broader Pipeline, and What Comes Next

Beyond retatrutide itself, the triple agonist concept is catalyzing a broader pipeline shift. Novo Nordisk's UBT251 and other candidates are advancing, and early-stage research is already exploring quadruple and quintuple agonist architectures. The direction is clear: metabolic pharmacology is moving from single-target precision toward multi-receptor orchestration.

For researchers working in adjacent areas, compounds like GLP-3 RT peptide variants and GLP Reta formulations represent the research-grade tools being used to probe these mechanisms at the preclinical level. Those evaluating GLP-3 peptide for sale options should prioritize purity-verified suppliers given the sensitivity of receptor binding studies.

Analyst outlook (speculative, clearly labeled as projections): If TRIUMPH-2 and TRIUMPH-3 read out positively in 2026 to 2027, regulatory submissions are anticipated by late 2027. Analysts broadly expect retatrutide to compete directly with tirzepatide and semaglutide in both obesity and type 2 diabetes indications, potentially capturing significant market share on the basis of superior weight loss magnitude.

Conclusion

The data emerging from Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design is not only advancing a single drug candidate, it is rewriting the rules for how metabolic trials are built. Longer durations, multi-system endpoints, and expanded inclusion criteria are now standard expectations rather than design innovations.

Actionable next steps for researchers and clinicians:

  1. Review the TRIUMPH and TRANSCEND-T2D-1 protocols to understand how multi-system endpoint selection is being operationalized.
  2. Evaluate whether existing study designs in obesity or MASLD research adequately capture hepatic and cardiovascular outcomes alongside weight.
  3. Monitor the broader triple agonist pipeline, UBT251 and emerging quintuple agonist candidates, for design precedents that may inform future protocol development.
  4. Source purity-verified research peptides from reputable suppliers when conducting preclinical receptor studies, ensuring data integrity from the outset.

The metabolic drug paradigm has shifted. Single-receptor thinking is giving way to coordinated multi-target strategies, and the trial infrastructure is following.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-and-glp-3-peptide-research-in-2026-how-triple-agonist-trials-are-res.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-13 13:04:022026-09-13 13:04:02Retatrutide and GLP-3 Peptide Research in 2026: How Triple Agonist Trials Are Reshaping Metabolic Study Design
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top