Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: triumph program

Retatrutide Dose-Escalation Research: Comparing Exposure, Tolerability, and Endpoint Timing Across Study Designs

Retatrutide Dose-Escalation Research: Comparing Exposure, Tolerability, and Endpoint Timing Across Study Designs

October 3, 2026/0 Comments/in Uncategorized/by

Roughly 26% of adults worldwide meet clinical criteria for obesity, yet fewer than half of those enrolled in weight-loss drug trials complete the full escalation phase without a dose reduction or dropout. That gap between protocol intent and real-world completion sits at the center of retatrutide dose-escalation research: comparing exposure, tolerability, and endpoint timing across study designs, and it is now driving a new generation of deliberately structured trials.

Key Takeaways

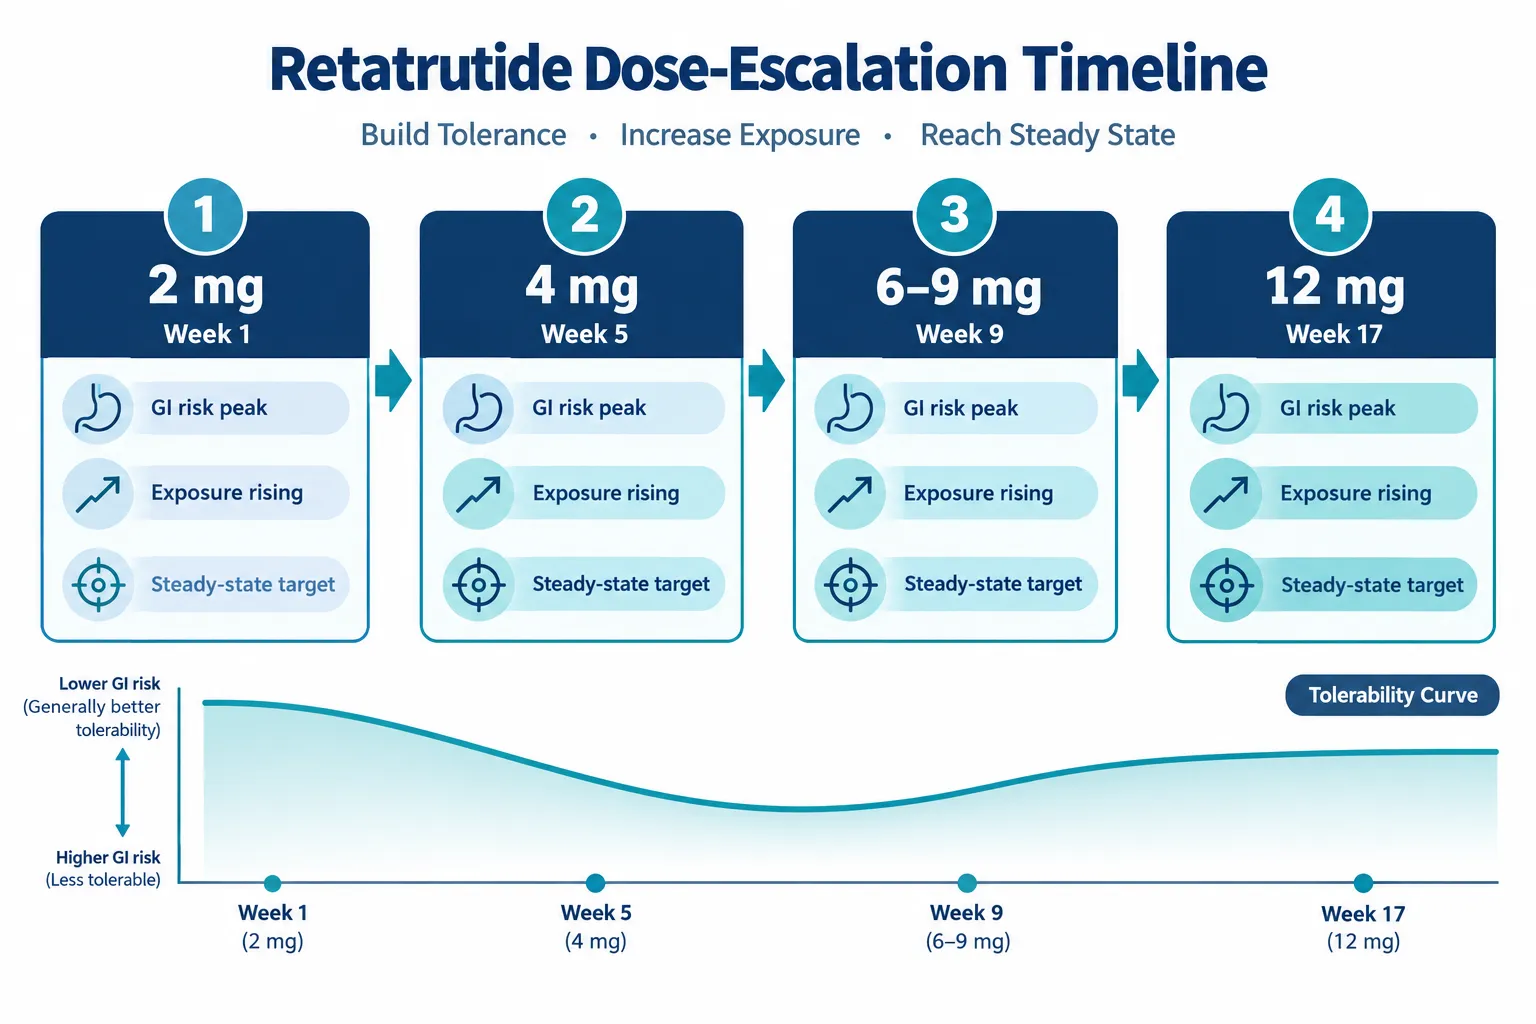
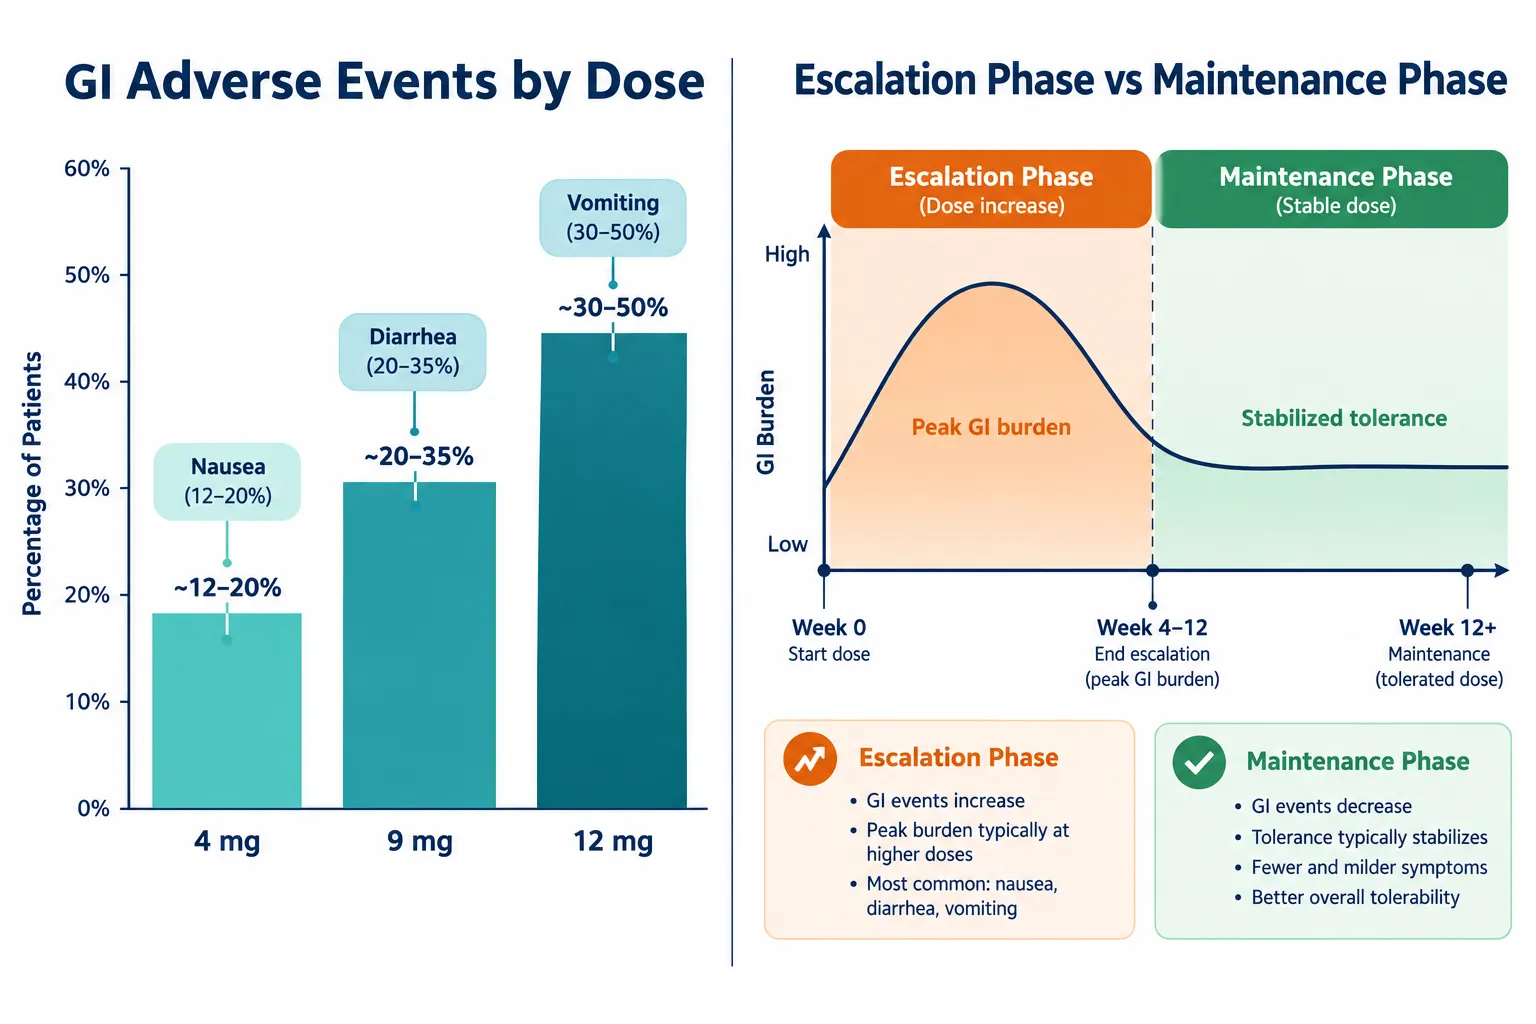
  • Retatrutide is titrated stepwise from 2 mg once weekly to target doses of 4, 9, or 12 mg, with escalation lasting approximately 16 weeks before a prolonged maintenance phase.
  • Gastrointestinal adverse events, nausea, diarrhea, and vomiting, are clearly dose-dependent and concentrate during the escalation phase rather than maintenance.
  • A dedicated phase 3b trial is directly comparing alternative escalation schedules to determine whether slower titration improves the efficacy-tolerability balance without sacrificing weight-loss outcomes.
  • Endpoint timing across studies is deliberately staggered: Week 24 captures early escalation impact, while 80-week designs assess long-term durability at steady-state exposure.
  • Emerging non-GI signals, including dysesthesia at the highest doses, are beginning to shape thinking about maximum recommended doses and future flexible titration labels.

How Escalation Schedules Shape Drug Exposure

The pharmacological foundation of any retatrutide dose-escalation study rests on a straightforward principle: the rate at which a participant reaches their target dose directly determines how quickly and how intensely the body is exposed to the drug's full activity. Retatrutide is a triple GIP, GLP-1, and glucagon receptor agonist, and its cardiometabolic mechanism differs meaningfully from classic small-molecule drugs.
How Escalation Schedules Shape Drug Exposure

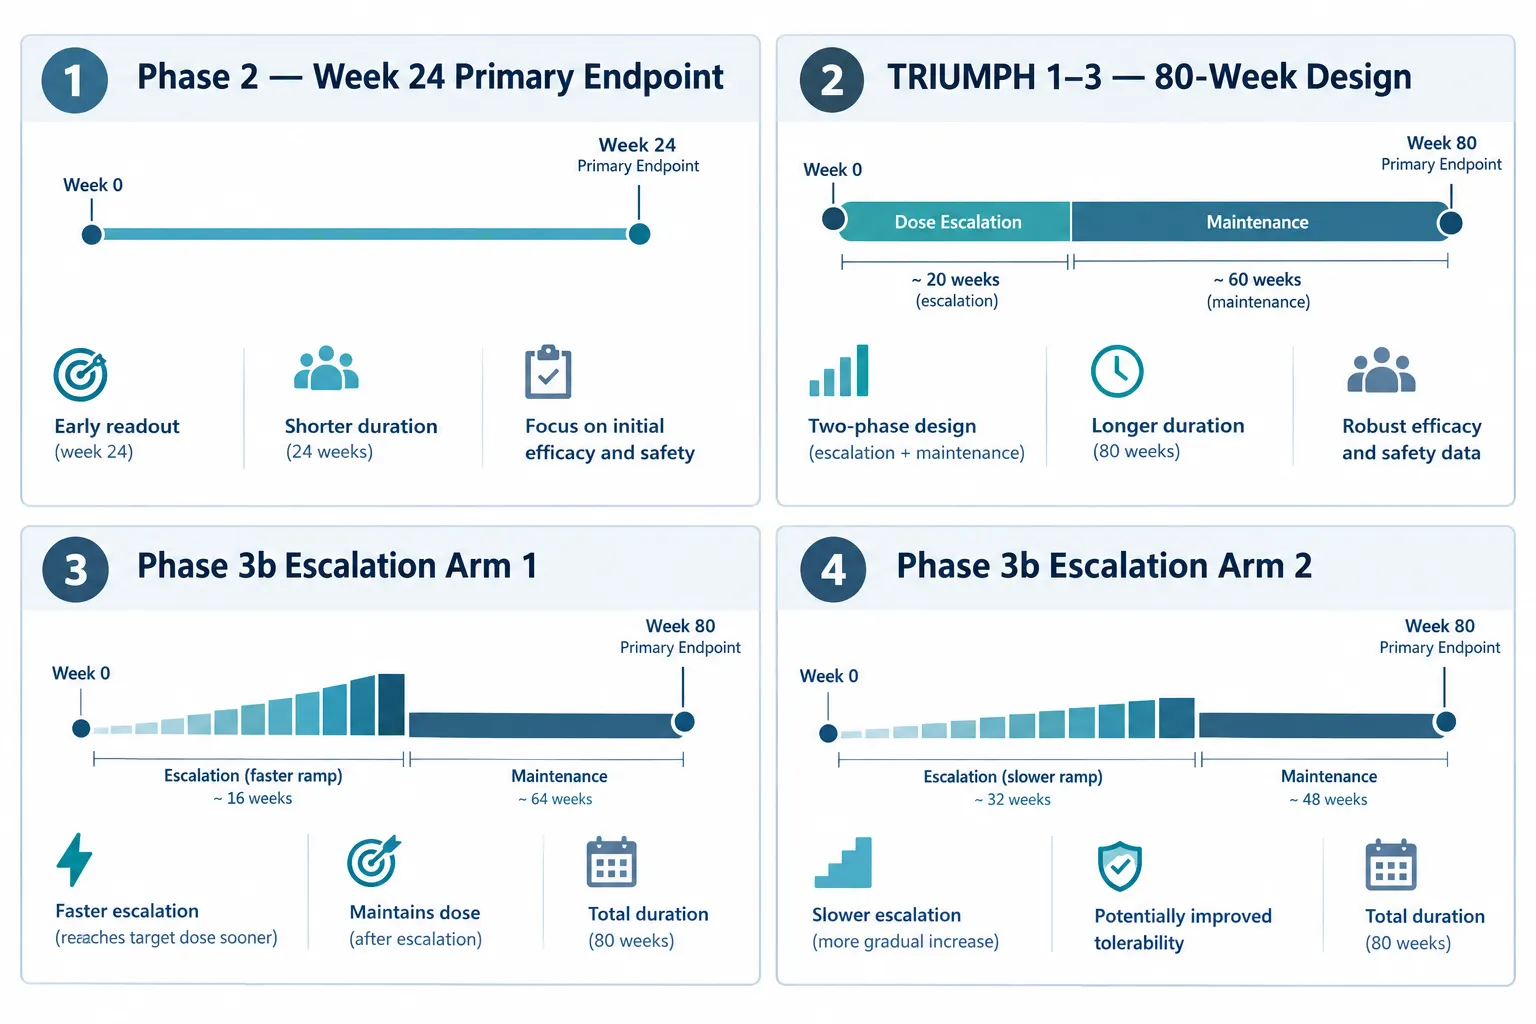
In the TRIUMPH program trials, the standard titration schedule moves participants from 2 mg once weekly to their assigned maintenance dose in four-weekly steps. The 4 mg arm requires only one step up (2 mg to 4 mg). The 9 mg arm moves through 2, 4, 6, and 9 mg over approximately 12 weeks. The 12 mg arm adds one further step to reach the ceiling dose, with escalation spanning roughly 16 weeks in total before a 64-week maintenance period begins.

This design has an important implication for exposure measurement. Participants spend a relatively short time in the escalation phase and a much longer time at steady-state. Any pharmacokinetic or pharmacodynamic endpoint measured early in the study reflects a rapidly changing exposure environment, while endpoints measured later reflect stable, high-exposure conditions. Comparing results across studies that use different escalation speeds therefore requires careful attention to when in the titration curve each measurement was taken.

Key exposure variables across escalation designs:

Design Feature Faster Escalation Slower Escalation
Time to target dose Shorter Longer
Peak early exposure Higher Lower
GI adverse event timing Earlier, more intense Spread over more weeks
Steady-state onset Earlier Delayed
Week 24 endpoint context Near or at maintenance Still escalating

Tolerability Data Across Dose Levels and Titration Speeds

The tolerability profile of retatrutide is one of the most closely tracked variables in current dose-escalation research. Across TRIUMPH program data, nausea was reported in approximately 16%, 20%, and 27% of participants at 4, 9, and 12 mg respectively, compared with under 4% on placebo. Diarrhea followed a similar gradient, rising from roughly 19% at 4 mg to 23% at 12 mg. Vomiting appeared in 16% to 18% of actively treated participants across dose levels.
Tolerability Data Across Dose Levels and Titration Speeds

At the highest tested doses, pooled safety analyses report nausea in up to 43% of participants, diarrhea in approximately 33%, and vomiting in around 21%. These figures are substantial, but discontinuation rates remained relatively low, 2.2% at 4 mg, 4.5% at 9 mg, and 5.1% at 12 mg, suggesting that most participants tolerate the burden, particularly when escalation is gradual.

The phase 2 obesity trial published in the New England Journal of Medicine provided early evidence that starting at 2 mg or 4 mg and increasing every four weeks meaningfully reduced GI symptom severity compared with more aggressive approaches. This finding now underpins the entire TRIUMPH escalation framework.

"Gastrointestinal adverse events are not only dose-related but also mitigated by starting at a lower dose and escalating gradually, a principle that is now being tested head-to-head in dedicated escalation-comparison trials."

Beyond GI symptoms, emerging data from TRIUMPH-4 topline results identified dysesthesia, abnormal skin sensations, in approximately 21% of participants at the highest dose. While GI events remain the primary tolerability concern, this non-GI signal is beginning to inform discussions about maximum recommended doses and the design of future long-duration studies.


Endpoint Timing and Study Design Across Current Trials

The most direct test of retatrutide dose-escalation research: comparing exposure, tolerability, and endpoint timing across study designs is now underway in a phase 3b trial registered in June 2026. This randomized, double-blind, parallel-assignment study includes at least two experimental arms, labeled "Retatrutide Dose Escalation 1" and "Retatrutide Dose Escalation 2", specifically designed to determine whether alternative titration schedules can shift the efficacy-tolerability balance without reducing the final maintenance dose.
Endpoint Timing and Study Design Across Current Trials

A multicenter phase 2 study adds further granularity. Participants are randomized to maintenance doses of 1, 4, 8, and 12 mg, but the 4 mg and 8 mg arms each include alternative escalation schedules to isolate the effect of titration speed from the effect of final dose. The primary endpoint, percent body weight change at Week 24, is strategically placed at a point when some participants will have just reached maintenance while others, on slower schedules, may still be escalating. This deliberate misalignment is not a flaw; it is the research question.

Why endpoint timing matters for interpretation:

  • Week 24 endpoints capture the combined effect of escalation intensity and early maintenance exposure, making them sensitive to titration speed differences.
  • Week 48 assessments provide extended anthropometric and safety data that reflect more stable exposure conditions.
  • 80-week TRIUMPH designs (16 weeks escalation plus 64 weeks maintenance) are built to evaluate long-term durability, metabolic improvements, and safety at sustained high-dose exposure.

This staggered endpoint strategy allows researchers and regulators to distinguish between the short-term impact of how fast a patient escalates and the long-term consequences of sustained high-dose therapy, two questions that earlier single-arm trials could not cleanly separate.

For context on how other research peptides approach dosing and timing considerations, the literature on SS-31 ideal dosage and timing illustrates how titration decisions affect both tolerability and endpoint interpretation across different compound classes. Similarly, CJC-1295 pharmacokinetic comparison research demonstrates how half-life and exposure curves shape study design choices more broadly.

Researchers interested in the broader RETA 10mg research context or the GLP3-RETA 20mg formulation will find that these product-level considerations connect directly to the dose-level questions being tested in current escalation trials.


Conclusion

Retatrutide dose-escalation research: comparing exposure, tolerability, and endpoint timing across study designs has moved from a secondary consideration to the central question of the current trial generation. The evidence is clear that slower titration reduces early GI burden without eliminating it, that adverse events are dose-dependent and concentrated in the escalation phase, and that endpoint timing must be interpreted relative to where each participant sits on their titration curve.

Actionable next steps for researchers and clinicians following this space:

  1. Track the phase 3b escalation-comparison trial results, which will provide the first head-to-head data on alternative titration schedules at identical maintenance doses.
  2. When reviewing published trial data, note the escalation schedule used and the timing of primary endpoints relative to when participants reached maintenance dose.
  3. Anticipate that future regulatory labels for retatrutide at 9-12 mg may embed flexible titration options rather than a single fixed schedule, based on the tolerability evidence accumulating in 2026 trials.
  4. Consider non-GI signals, particularly dysesthesia at the highest doses, as part of the full exposure-tolerability profile when evaluating study designs.

The field is moving toward individualized titration, not as a clinical convenience, but as a scientifically validated strategy supported by rigorously designed comparative trials.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-dose-escalation-research-comparing-exposure-tolerability-and-endpoin.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-03 13:08:342026-10-03 13:08:34Retatrutide Dose-Escalation Research: Comparing Exposure, Tolerability, and Endpoint Timing Across Study Designs
Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols

Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols

September 24, 2026/0 Comments/in Uncategorized/by

By August 2026, a key obesity Phase 3 study within the TRIUMPH program was officially marked as completed in clinical trial registries, a milestone that is already forcing researchers to rethink how they design, benchmark, and report nonclinical studies involving metabolic peptides. The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols conversation is no longer speculative. The data are in, and they are reshaping the field.

Key Takeaways

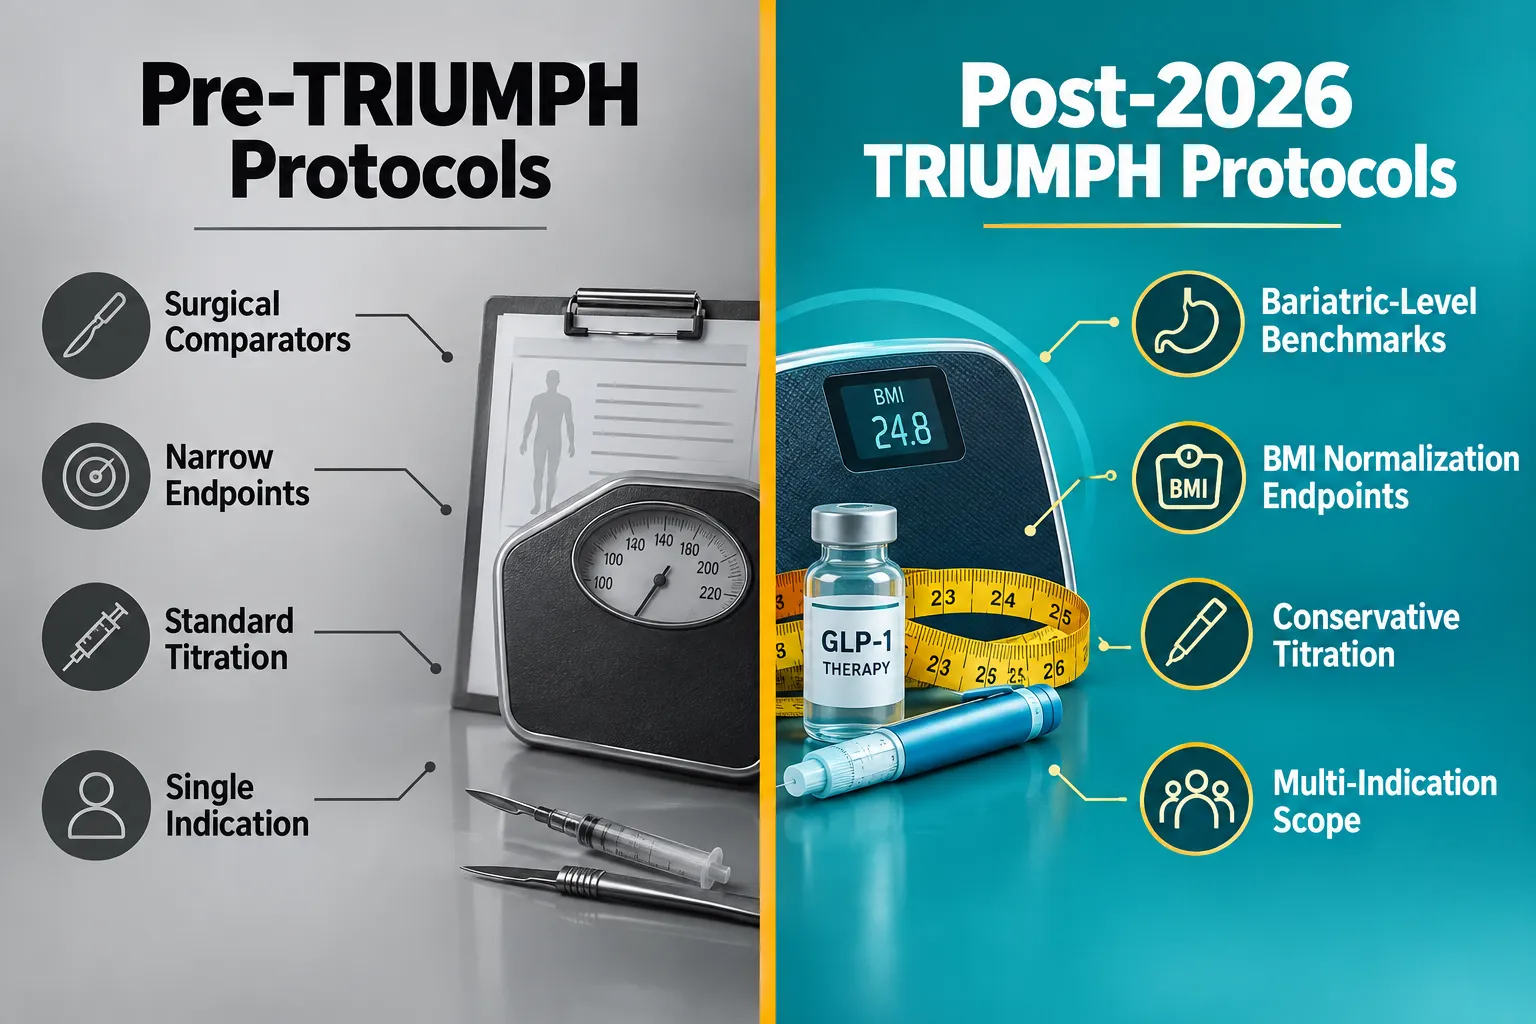
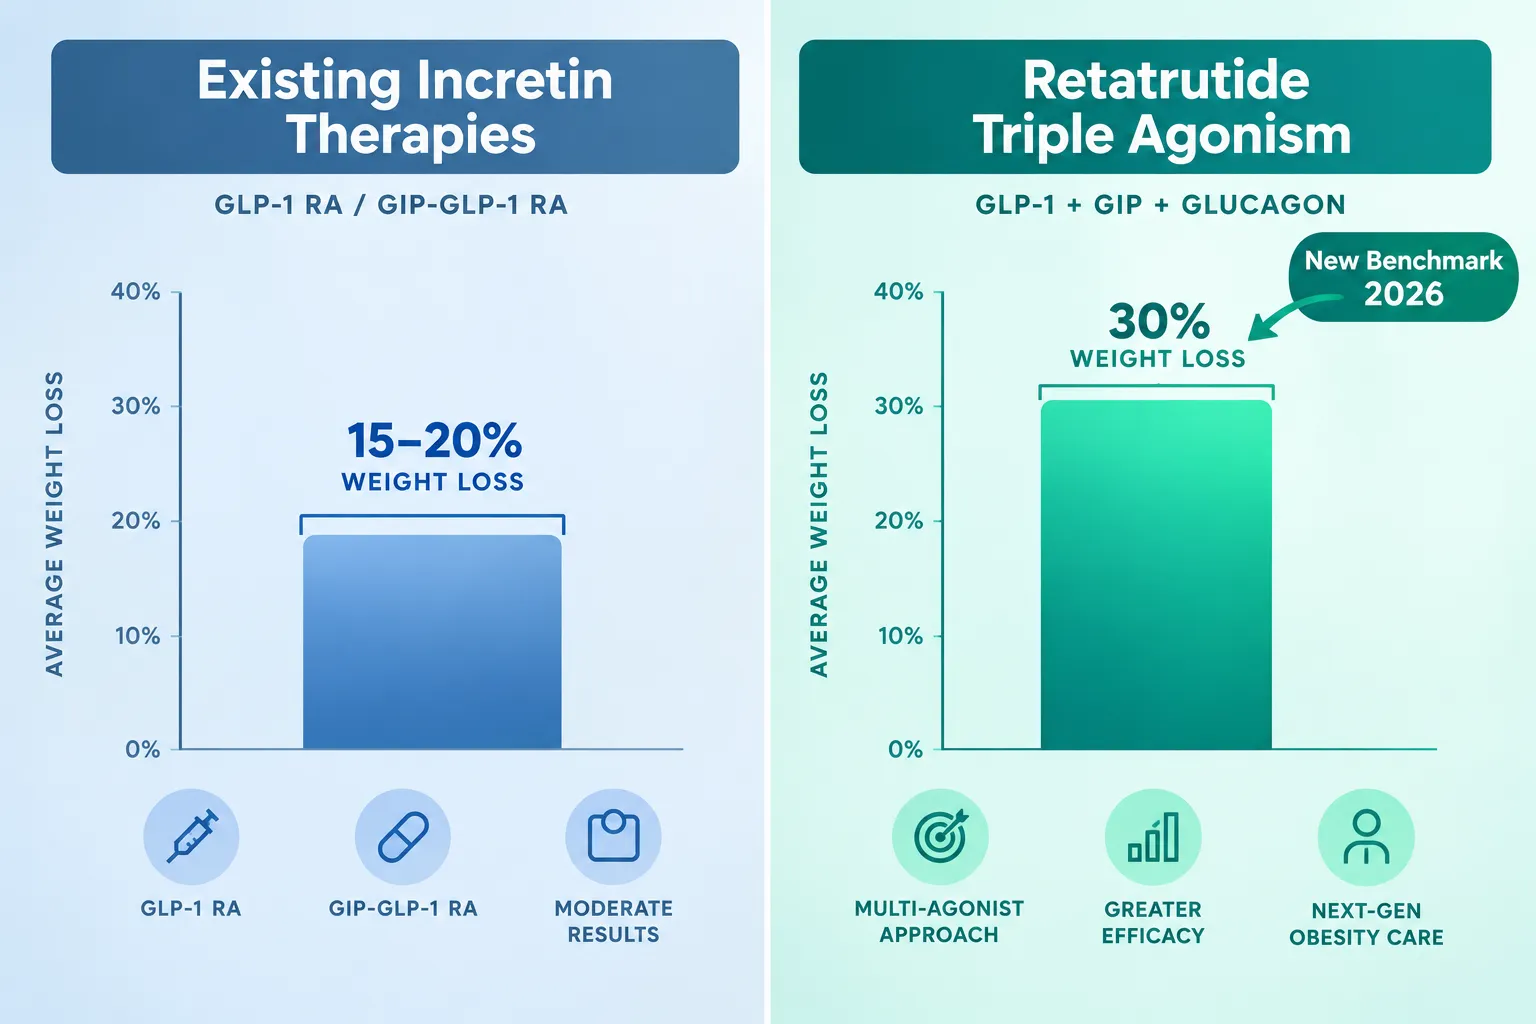
  • Retatrutide's TRIUMPH Phase 3 program has produced weight-loss outcomes of up to 30% at 104 weeks, approaching bariatric surgery benchmarks.
  • Dual efficacy on body weight and glycemic control (up to 1.9-point A1c reduction) makes single-endpoint trial designs increasingly inadequate.
  • Conservative titration schedules and improved retention strategies are now a protocol necessity, not an option.
  • Multi-indication Phase 3 data covering knee OA, OSA, MASLD, and cardiovascular outcomes are expanding the scope of required comparator arms.
  • Retatrutide remains investigational as of late 2026, meaning all research use is subject to regulatory-oriented trial design standards.

The TRIUMPH Program: A Phase 3 Snapshot That Changes Benchmarks

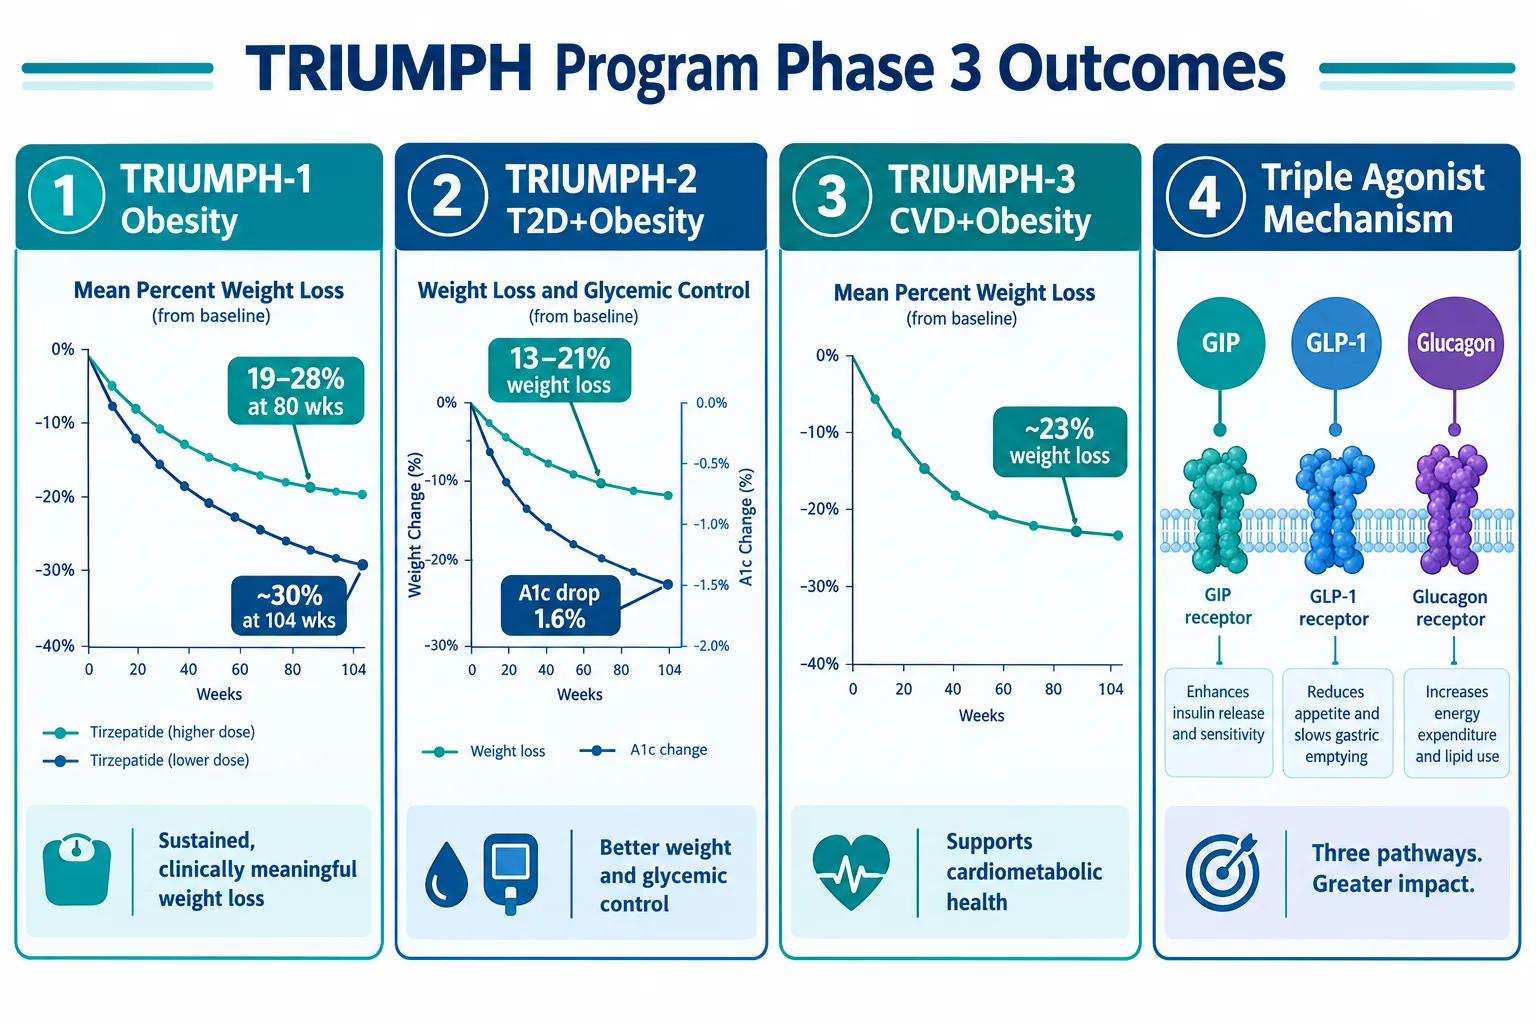
Retatrutide is a first-in-class triple agonist targeting GIP, GLP-1, and glucagon receptors simultaneously. That triple mechanism is what separates it from existing approved therapies and from earlier dual-agonist candidates. For researchers working with retatrutide clinical trial data, the TRIUMPH program now provides the most complete Phase 3 picture available for any triple agonist.

The TRIUMPH Program: A Phase 3 Snapshot That Changes Benchmarks

The headline numbers are striking:

  • TRIUMPH-1 (obesity without diabetes): approximately 19-28% weight loss at 80 weeks, rising to roughly 30% at 104 weeks.
  • TRIUMPH-2 (obesity with type 2 diabetes): 13-21% weight loss plus up to a 1.6% A1c reduction over 80 weeks.
  • TRIUMPH-3 (severe obesity with established cardiovascular disease): approximately 23% weight loss with manageable discontinuation rates.

"Bariatric-like efficacy from a weekly injectable peptide is no longer a theoretical ceiling, TRIUMPH-3 data make it a documented outcome."

These figures introduce what some analysts are calling "de-obesification" endpoints, a term reflecting the normalization of BMI as a primary outcome rather than a secondary marker. For anyone reviewing GLP-1 Reta or GLP-3 Reta research-use compounds, understanding this endpoint shift is essential context.


How the 2026 Obesity and Diabetes Data Rewrites Protocol Design

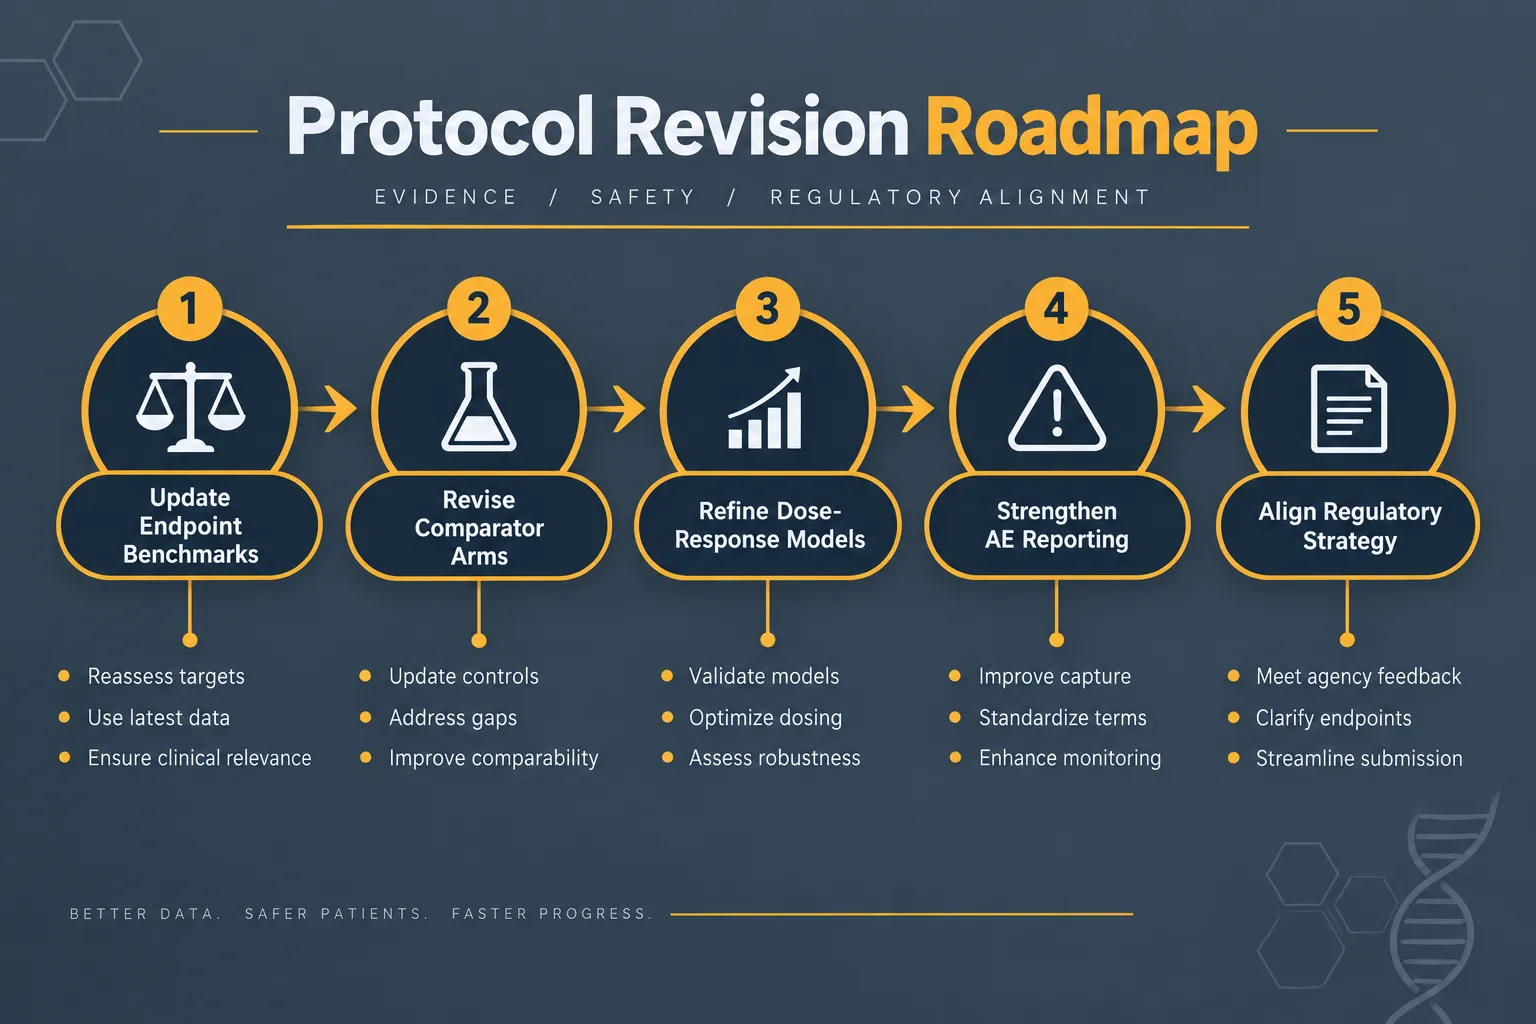
The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols discussion centers on four concrete areas where existing study designs are now outdated.

1. Endpoint Selection

Single-endpoint designs that measure only weight or only glycemic control are no longer sufficient when the reference compound achieves both simultaneously. Researchers should now plan co-primary endpoints that capture:

  • Percent total body weight loss
  • A1c reduction
  • Cardiometabolic markers (blood pressure, lipids, inflammatory markers)
  • BMI normalization rates

2. Comparator Arm Selection

TRIUMPH data push the efficacy bar to near-surgical levels. Using older GLP-1 monotherapies as the sole active comparator now risks underestimating effect size. Protocol designers should consider:

Comparator Type Relevance Post-TRIUMPH
Older GLP-1 monotherapy Insufficient ceiling for effect-size modeling
Dual agonist (e.g., tirzepatide) Appropriate active comparator
Bariatric surgery outcomes Now a legitimate benchmark arm
Placebo only Acceptable but limits translational value

For broader context on how peptide mechanisms interact with metabolic pathways, the Peptides 101 for Research-Use Only Buyers resource provides a useful structural overview.

3. Dose-Response Modeling

3. Dose-Response Modeling

TRIUMPH safety data revealed that aggressive titration schedules drove higher discontinuation rates. This finding is directly actionable for nonclinical protocol design. Dose-response models should now incorporate:

  • Extended low-dose phases before escalation
  • Plateau detection windows to identify responders before maximum dosing
  • Dropout probability curves built from TRIUMPH discontinuation patterns

Researchers using Reta 10mg formulations in nonclinical settings should map titration schedules against TRIUMPH's published escalation timelines to ensure their models remain translatable.

4. Adverse-Event Reporting Standards

The TRIUMPH program's safety profile, primarily gastrointestinal events, has established a new floor for what must be captured and reported. Nonclinical adverse-event frameworks should now include structured tracking for:

  • Nausea and vomiting incidence by dose level
  • Time-to-onset relative to titration step
  • Severity grading aligned with TRIUMPH's published criteria

Expanding Scope: Multi-Indication Data and What Comes Next

The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols story does not end with weight and glycemia. The TRIUMPH program includes at least seven additional Phase 3 datasets expected through 2026-2027, covering knee osteoarthritis, obstructive sleep apnea, metabolic-associated steatotic liver disease (MASLD), chronic pain, and cardiovascular-renal outcomes.

Expanding Scope: Multi-Indication Data and What Comes Next

This multi-indication expansion has two immediate implications for protocol designers:

  1. Organ-specific endpoints (liver stiffness scores, AHI reductions, joint function scales) will need to be incorporated into metabolic research designs that previously focused only on weight.
  2. Comparator arms will need to account for condition-specific active controls, not just metabolic benchmarks.

Researchers working in adjacent areas, such as mitochondrial function studies or growth hormone secretagogue research, should note that Tesamorelin data on visceral fat reduction may serve as a useful secondary comparator in MASLD-adjacent protocols.


Conclusion

The TRIUMPH Phase 3 program has fundamentally changed the reference frame for metabolic research protocols. Researchers who continue using pre-2026 endpoint structures, outdated comparator arms, or aggressive titration schedules will produce data that are difficult to interpret against the current evidence base.

Actionable next steps for protocol teams:

  1. Audit existing endpoint frameworks against TRIUMPH co-primary outcomes and add cardiometabolic markers where absent.
  2. Replace or supplement older GLP-1 monotherapy comparators with dual-agonist or bariatric-surgery benchmarks.
  3. Build conservative titration schedules into dose-response models and document dropout probability curves.
  4. Expand adverse-event capture to include time-to-onset data aligned with TRIUMPH's published safety criteria.
  5. Monitor the seven additional TRIUMPH Phase 3 readouts expected through 2027 and update protocols as each dataset publishes.

Retatrutide remains investigational as of late 2026. All research use must align with regulatory-oriented trial design standards. The data, however, are no longer a moving target, and protocol teams that adapt now will be best positioned when regulatory submissions begin.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-phase-3-results-in-2026-what-the-new-obesity-and-diabetes-data-chang.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-24 13:05:072026-09-24 13:05:07Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols
Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols

Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols

September 18, 2026/0 Comments/in Uncategorized/by

Nearly one billion adults worldwide live with obesity, and for decades, no pharmacological agent came close to matching the weight reduction achieved by bariatric surgery. That benchmark is now being challenged. The Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols represents a pivotal moment in metabolic medicine, with topline results from the TRIUMPH program reshaping how researchers and clinicians think about next-generation weight management strategies.

Key Takeaways

  • Retatrutide is the first triple incretin agonist, targeting GLP-1, GIP, and glucagon receptors simultaneously, to reach large-scale Phase 3 evaluation.
  • TRIUMPH-1 topline data released May 2026 showed up to approximately 30% body weight reduction over two years at the highest dose.
  • The TRIUMPH program spans obesity, type 2 diabetes, sleep apnea, osteoarthritis, cardiovascular, and liver outcomes.
  • Titration protocols emerging from TRIUMPH-1 are informing 2026 laboratory research models and preclinical study designs.
  • Retatrutide sets a new comparative efficacy benchmark against existing dual incretin therapies such as tirzepatide.

Understanding the Triple Incretin Mechanism Behind 2026 Protocol Design

Understanding the Triple Incretin Mechanism Behind 2026 Protocol Design

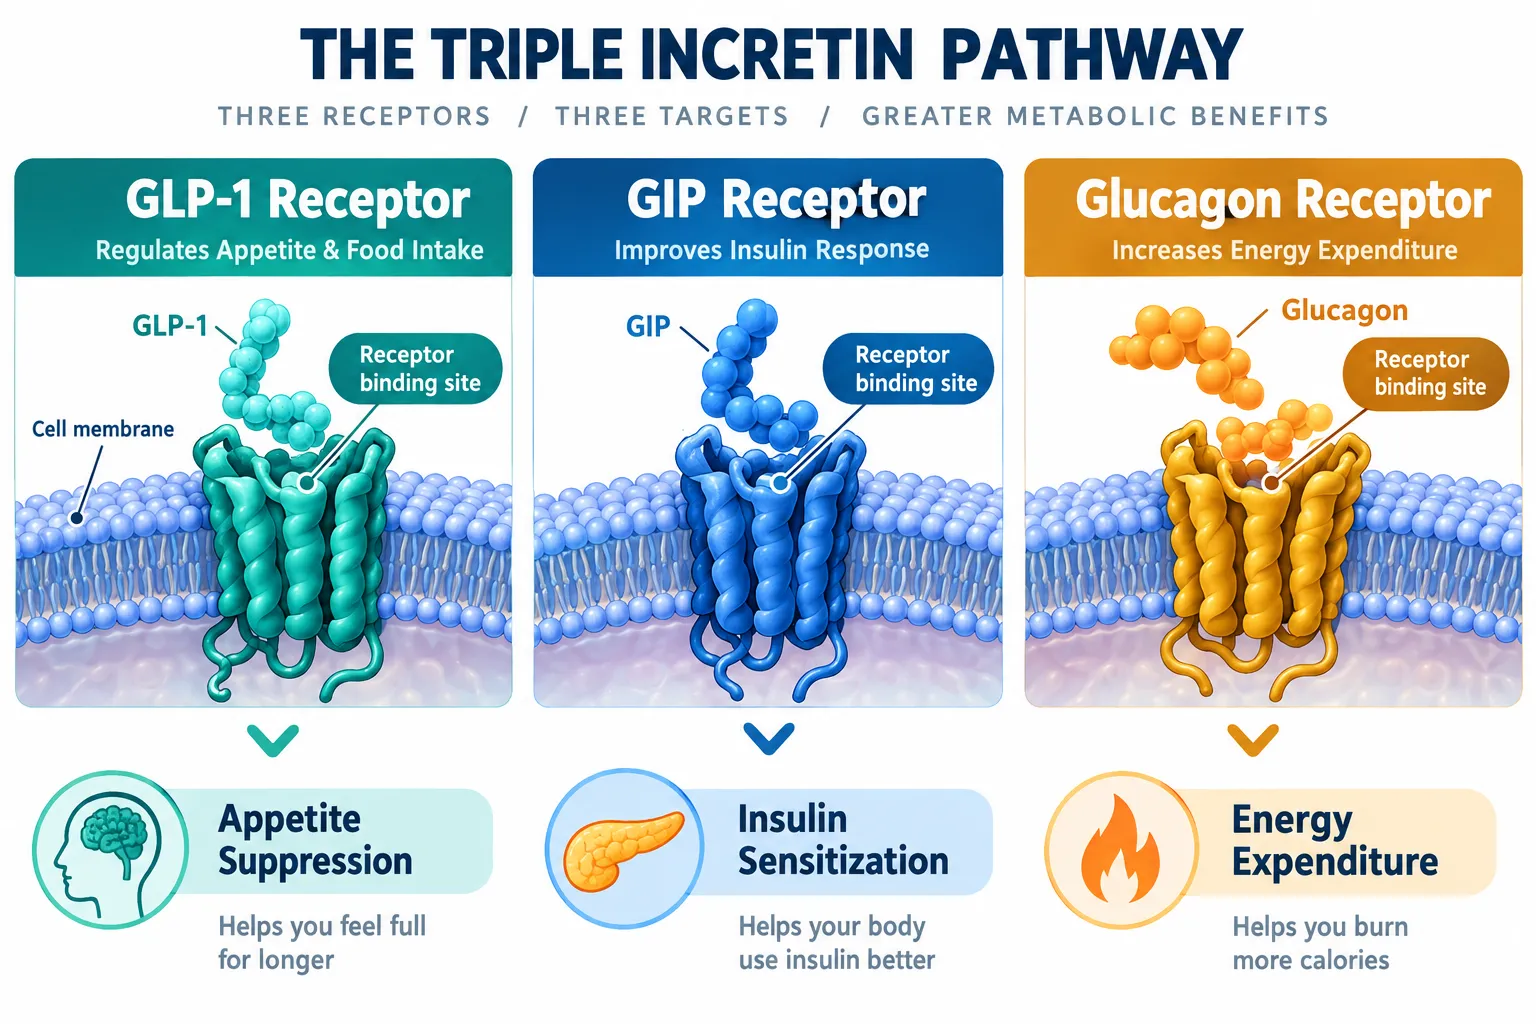
Retatrutide's pharmacological profile is built on simultaneous agonism at three distinct receptors. Understanding this tri-receptor architecture is essential for interpreting the Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols in a meaningful way.

The three receptor targets work in coordinated synergy:

Receptor Primary Metabolic Role Contribution to Weight Loss
GLP-1 Appetite suppression, gastric emptying Reduces caloric intake
GIP Insulin sensitization, fat metabolism Enhances glucose disposal
Glucagon Energy expenditure, hepatic glucose output Increases caloric burn

Where GLP-1 receptor agonists like semaglutide act on a single pathway, and tirzepatide engages two, retatrutide's glucagon component adds a thermogenic dimension. This third axis drives energy expenditure independent of caloric restriction, a mechanistic advantage that researchers are now incorporating into cardiometabolic peptide research models.

The glucagon receptor component also accelerates hepatic fat clearance, making retatrutide particularly relevant for metabolic dysfunction-associated steatotic liver disease (MASLD) endpoints now embedded in the TRIUMPH program.

For researchers sourcing compounds for preclinical models, GLP-3 Reta CAG 10mg represents one formulation used in controlled laboratory settings to study this tri-agonist activity.

TRIUMPH Program: Phase 3 Trial Data Updates Across Six Indication Areas

TRIUMPH Program: Phase 3 Trial Data Updates Across Six Indication Areas

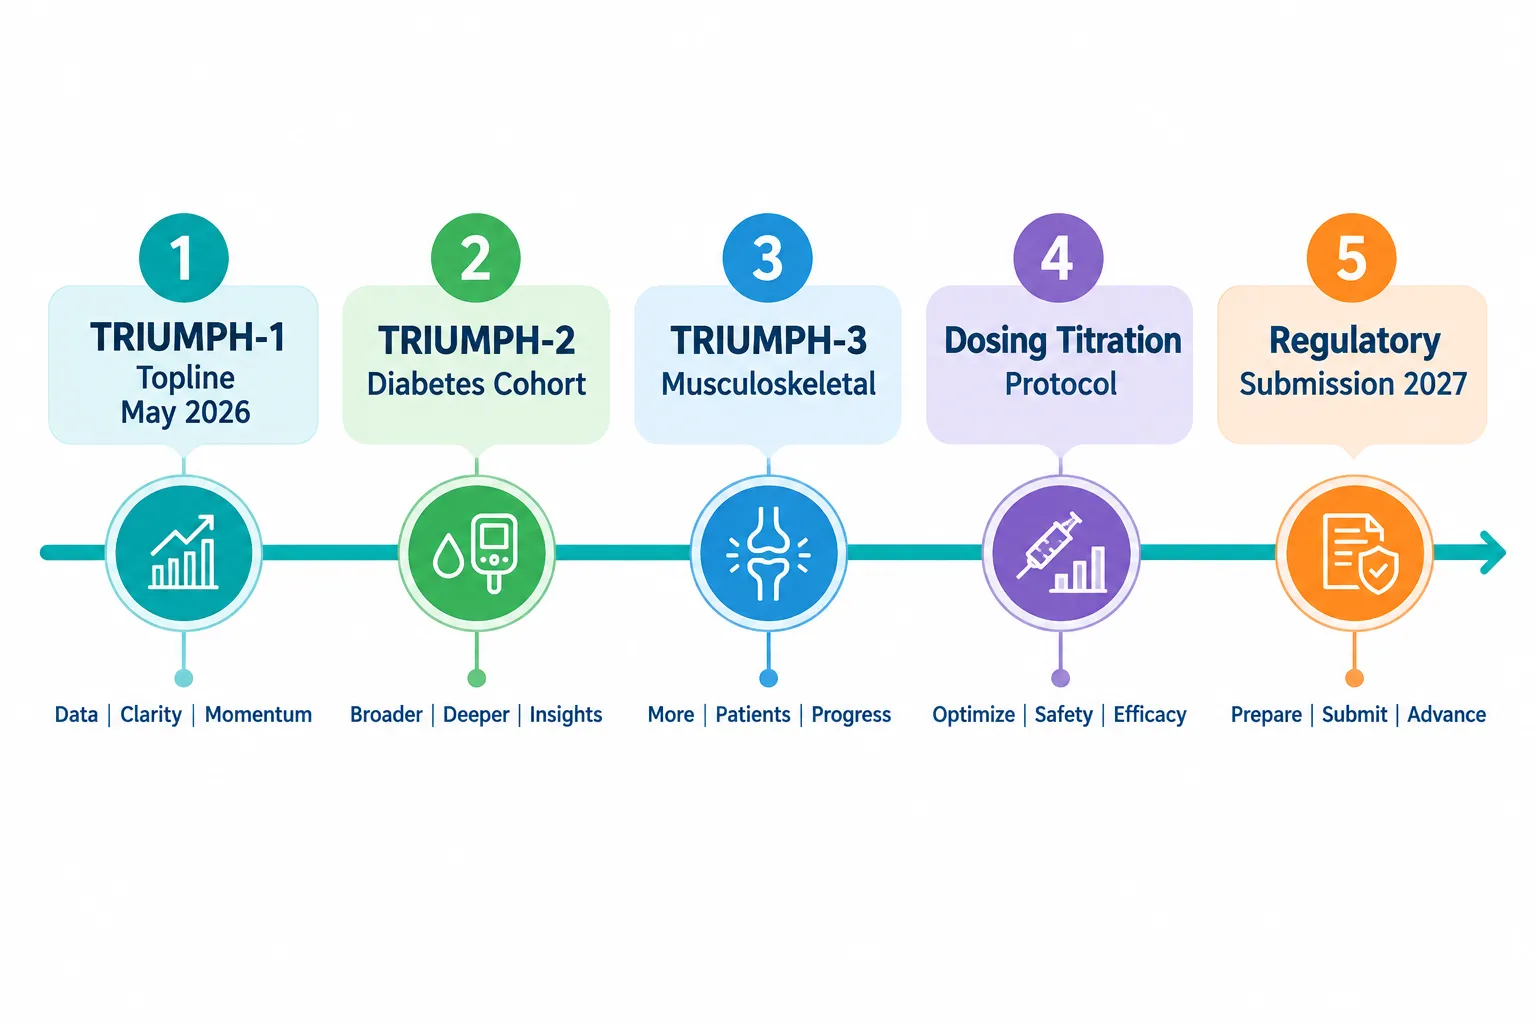
The TRIUMPH program is the most expansive Phase 3 obesity trial program launched for any incretin-based therapy. As of September 2026, six distinct trial arms are active or reporting:

TRIUMPH-1 delivered topline results in May 2026. Participants receiving the highest dose achieved approximately 30% mean body weight reduction over 96 weeks, a figure that exceeds any approved pharmacotherapy currently on the market. Dose-response data confirmed a clear gradient: lower doses produced 20-24% reductions, while the highest titrated dose consistently approached the 30% threshold.

TRIUMPH-2 is the diabetes-specific arm, spotlighted at the EASD 2026 conference. This cohort examines retatrutide in adults with obesity and comorbid type 2 diabetes, where the GIP and glucagon components are expected to deliver additive glycemic benefit beyond what GLP-1 agonism alone provides.

TRIUMPH-3 addresses a frequently overlooked comorbidity: musculoskeletal disease. Early data suggest that weight loss of 20-30% produces clinically meaningful reductions in osteoarthritis pain scores, a finding with direct implications for retatrutide endpoints research design.

Additional arms cover obstructive sleep apnea, cardiovascular outcomes, and liver disease, broadening the clinical utility profile well beyond weight reduction alone.

"A 30% reduction in body weight from a subcutaneous weekly injection would have been considered implausible a decade ago. TRIUMPH-1 has changed that calculus entirely."

Comparative Efficacy and 2026 Protocol Implications for Research Models

Comparative Efficacy and 2026 Protocol Implications for Research Models

The Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols has direct consequences for how preclinical and translational researchers structure their metabolic models going forward.

Dosing and titration insights from TRIUMPH-1 show a gradual 24-week escalation protocol reaching a maximum dose of 12 mg weekly. This slow titration minimizes gastrointestinal adverse events, the primary tolerability concern with incretin therapies, while allowing receptor adaptation. Researchers designing laboratory protocols in 2026 are mapping these titration curves to animal model equivalents.

Comparative context matters. Semaglutide at 2.4 mg produces roughly 15-17% weight loss. Tirzepatide achieves approximately 20-22%. Retatrutide's ~30% positions it in a category of its own, approaching surgical outcomes without procedural risk. For those studying GLP-1 Reta formulations in metabolic research, this efficacy differential demands updated experimental benchmarks.

Researchers working with higher-dose models can explore GLP-3 Reta 20mg GSF and GLP-3 Reta 20mg GA1 formulations designed for controlled preclinical studies. Those requiring larger quantities for extended protocols may reference GLP-3 Reta 30mg options.

Key protocol design considerations for 2026 research:

  • Incorporate glucagon receptor activity into metabolic outcome measurements
  • Align titration schedules with TRIUMPH-1 escalation data
  • Include liver fat, inflammatory markers, and joint-loading endpoints alongside body composition
  • Account for the extended durability window, two-year data shows sustained, not plateauing, weight loss

Predicted 2027 outlook (speculative): If regulatory submissions proceed following anticipated 2026 data lock milestones, retatrutide could enter FDA review in 2027. Approval would likely trigger a rapid repositioning of existing obesity treatment algorithms across clinical and research settings alike.

Conclusion

The TRIUMPH program's 2026 data outputs have fundamentally repositioned retatrutide as the leading candidate in next-generation obesity pharmacotherapy. The triple incretin mechanism, GLP-1, GIP, and glucagon working in concert, delivers weight loss outcomes that no single or dual agonist has matched in controlled Phase 3 conditions.

Actionable next steps for researchers and protocol designers:

  1. Review TRIUMPH-1 titration schedules and adapt dose-escalation models to preclinical study designs.
  2. Expand endpoint panels to include hepatic, musculoskeletal, and cardiovascular markers consistent with the TRIUMPH program's breadth.
  3. Update comparative benchmarks in metabolic research models to reflect the new ~30% weight loss standard.
  4. Monitor TRIUMPH-2 diabetes cohort data from EASD 2026 for glycemic endpoint integration.
  5. Source validated research-grade compounds through verified suppliers to ensure experimental reproducibility.

The science of incretin tri-agonism is no longer theoretical, it is producing real, reproducible, and historically significant clinical outcomes in 2026.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-phase-3-obesity-trial-data-updates-triple-incretin-mechanism-analysi.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-18 13:04:472026-09-18 13:04:47Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols

Tag Archive for: triumph program

Retatrutide Clinical Trials Explained: Phase 2 to Phase 3 Outcomes, Endpoints, and What Researchers Should Track

Retatrutide Clinical Trials Explained: Phase 2 to Phase 3 Outcomes, Endpoints, and What Researchers Should Track

June 14, 2026/0 Comments/by Pure Tested

A drug that produces roughly 28% average body weight loss in 18 months — approaching outcomes typically associated with bariatric surgery — demands a clear-eyed reading of the trial record behind it. That is exactly what this guide delivers. Understanding the Retatrutide Clinical Trials Explained: Phase 2 to Phase 3 Outcomes, Endpoints, and What Researchers Should Track framework helps researchers, clinicians, and informed readers interpret efficacy data, dose-escalation patterns, and cardiometabolic endpoints without getting lost in trial jargon.

Key Takeaways

  • Retatrutide is a once-weekly triple agonist targeting GLP-1, GIP, and glucagon receptors simultaneously.
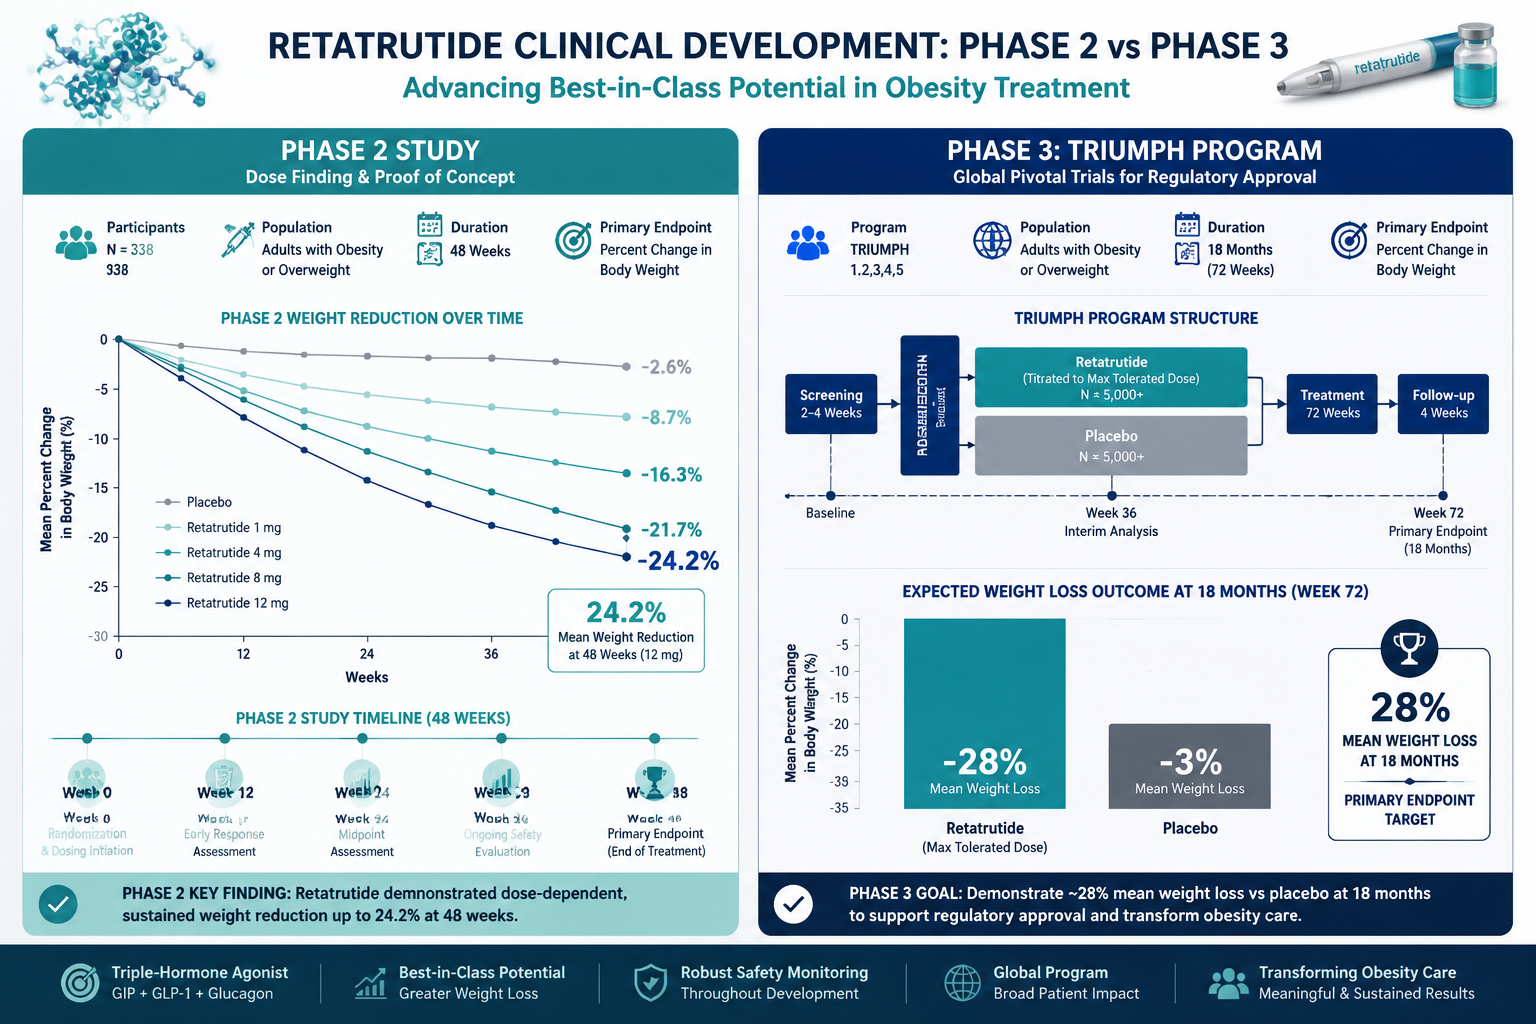
  • Phase 2 trials showed up to 24.2% weight reduction at 48 weeks; Phase 3 data now shows approximately 28% over 18 months.
  • The TRIUMPH Phase 3 program spans obesity, type 2 diabetes, knee osteoarthritis, and obstructive sleep apnea.
  • Gastrointestinal adverse events are the most common safety signal, with discontinuation rates of 12-18% at higher doses.
  • Researchers should track both primary efficacy endpoints and secondary cardiometabolic biomarkers across dose cohorts.

Key Takeaways

From Phase 2 to Phase 3: How the Trial Record Builds

The Retatrutide Clinical Trials Explained: Phase 2 to Phase 3 Outcomes, Endpoints, and What Researchers Should Track story begins with mechanism. Retatrutide activates three receptors — GLP-1, GIP, and glucagon — in a single once-weekly subcutaneous injection. This triple-agonist profile distinguishes it from earlier GLP-1 mono-agonists and dual agonists. For context on how GLP-1 receptor pharmacology has evolved across generations, the GLP-1 generations overview provides useful background, and a deeper look at dual receptor agonism in research shows why adding a third receptor target changes the efficacy ceiling.

Phase 2 results published in a landmark study demonstrated a mean weight reduction of up to 24.2% at 48 weeks in adults with obesity or overweight without diabetes. Crucially, this was dose-dependent: participants on higher dose arms consistently outperformed those on lower doses, establishing the dose-escalation rationale that Phase 3 protocols would formalize.

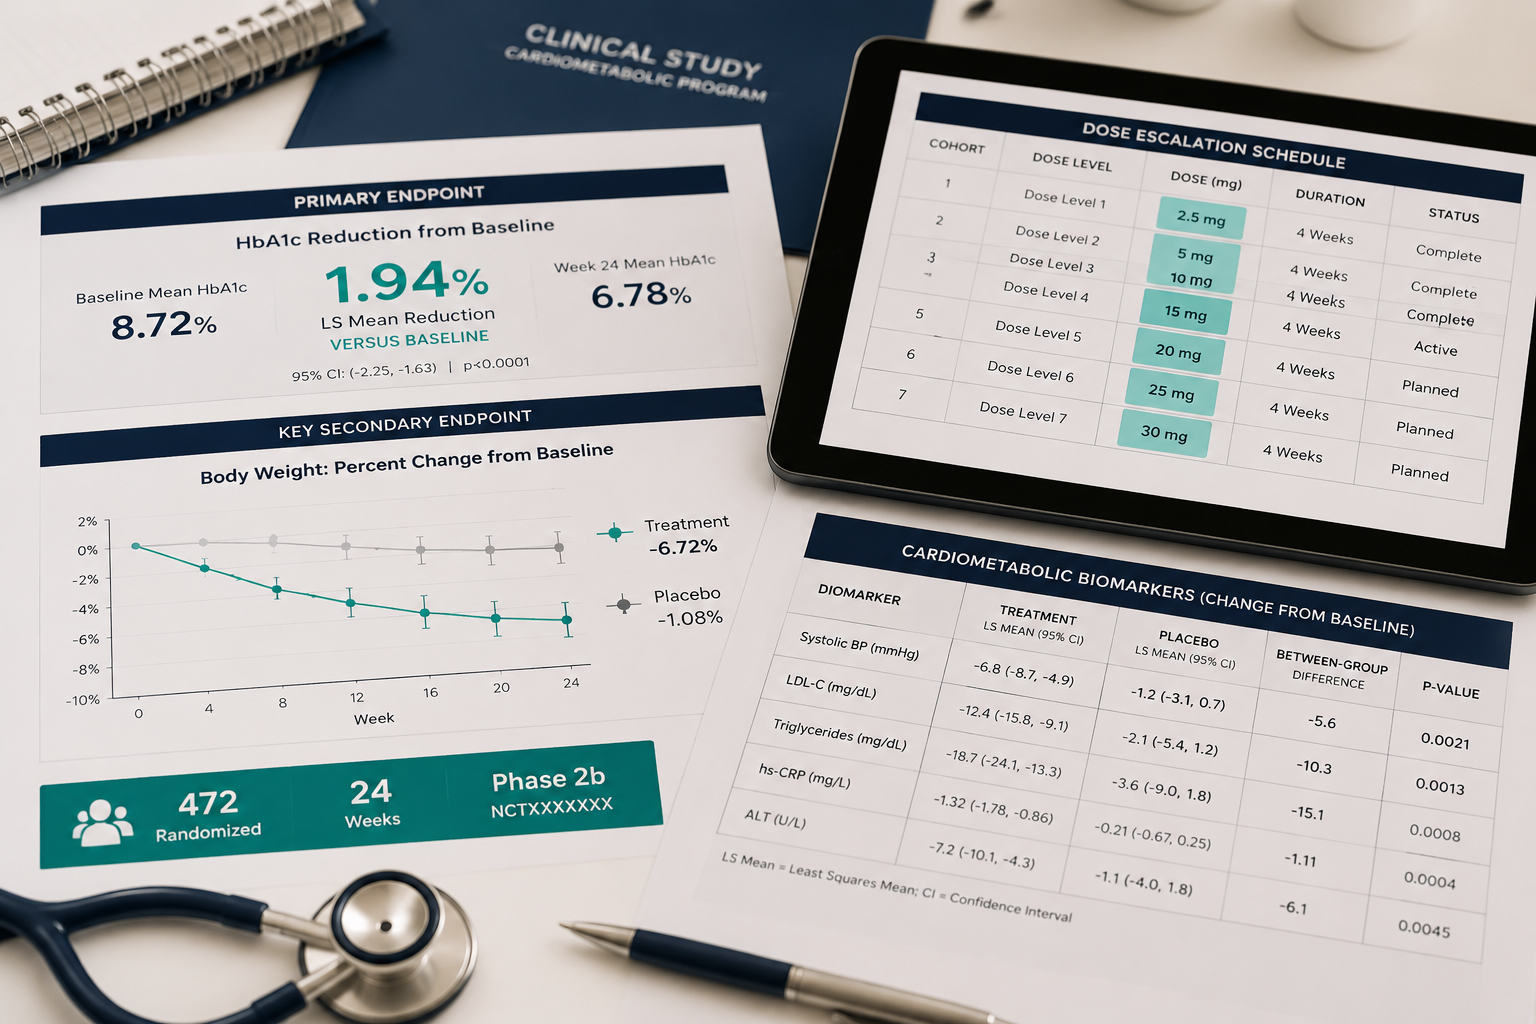
Phase 3 results from the TRIUMPH program have now confirmed and extended those findings. In an obesity-focused trial, retatrutide produced approximately 28% average weight loss over 18 months — a figure that rivals surgical intervention. The TRANSCEND-T2D-1 Phase 3 trial in type 2 diabetes reported a mean HbA1c reduction of 1.94% alongside a 15.3% decrease in body weight over 40 weeks in adults inadequately controlled by diet and exercise alone.

Trial Phase Population Duration Key Outcome
Phase 2 Obesity/Overweight (no T2D) 48 weeks Up to 24.2% weight loss
Phase 3 (TRIUMPH) Obesity 18 months ~28% weight loss
Phase 3 (TRANSCEND-T2D-1) Type 2 Diabetes 40 weeks 1.94% HbA1c reduction, 15.3% weight loss

From Phase 2 to Phase 3: How the Trial Record Builds

Endpoints and Cardiometabolic Outcomes Researchers Must Prioritize

When reading any retatrutide trial report, distinguishing primary endpoints from secondary and exploratory endpoints is essential.

Primary efficacy endpoints in obesity trials are typically:

  • Percentage change in body weight from baseline
  • Proportion of participants achieving 5%, 10%, or 15% weight loss thresholds

Secondary endpoints that carry significant clinical weight include:

  • Waist circumference reduction
  • Fasting glucose and insulin sensitivity markers
  • HbA1c trajectory (especially in metabolic subgroups)
  • Lipid panel changes (LDL, triglycerides, HDL)
  • Blood pressure and resting heart rate

Cardiometabolic outcomes deserve special attention because glucagon receptor activation — the component that separates retatrutide from tirzepatide — appears to amplify energy expenditure and lipid mobilization beyond what GLP-1/GIP alone achieves. Researchers tracking these outcomes should note that the TRIUMPH program also evaluates retatrutide across knee osteoarthritis pain and obstructive sleep apnea, with over 5,800 participants enrolled across indications. This breadth is unusual and signals confidence in the mechanism's systemic reach.

For researchers interested in how metabolic peptides interact with body composition endpoints more broadly, the tesa body composition research themes page offers a useful parallel in lipid mobilization science, and lipid mobilization research themes provides additional mechanistic context.


Endpoints and Cardiometabolic Outcomes Researchers Must Prioritize

Safety Signals, Dose Escalation, and What the Data Shows

The safety profile of retatrutide follows a pattern familiar to GLP-1 class agents but with important nuances researchers should document carefully.

Most common adverse events:

  • Nausea
  • Diarrhea
  • Vomiting
  • Constipation

Discontinuation rates due to adverse events ranged from approximately 12-18% at higher doses, compared to roughly 4% with placebo. This gap is clinically meaningful and underscores why dose-escalation schedules matter. Trials used gradual titration — starting at lower milligram doses and stepping up over weeks — to improve tolerability. Researchers reviewing trial data should always note which dose arm a participant was in when an adverse event occurred, as pooling across arms obscures this signal.

"The dose-escalation pattern in retatrutide trials is not incidental — it is the primary tool for balancing efficacy against gastrointestinal tolerability."

Regulatory momentum is building. Eli Lilly plans to seek FDA approval for retatrutide, potentially before the end of 2026, pending completion of remaining TRIUMPH trial arms. For researchers following the broader GLP-1 triple agonist landscape, retatrutide represents the most advanced compound in this class currently in late-stage development. Those sourcing research-grade reference compounds can also explore the retatrutide product tag and GLP-1 research peptide category for laboratory use context.


Conclusion

The Retatrutide Clinical Trials Explained: Phase 2 to Phase 3 Outcomes, Endpoints, and What Researchers Should Track framework comes down to three practical actions. First, always read trial results stratified by dose arm — aggregate numbers hide the dose-response relationship that defines this compound. Second, track secondary cardiometabolic endpoints alongside primary weight outcomes; the glucagon receptor component makes these particularly informative. Third, monitor the TRIUMPH program's remaining readouts on sleep apnea and osteoarthritis, which will determine how broadly retatrutide's label is eventually written. As 2026 progresses toward a likely FDA submission, the trial record already makes one thing clear: triple-receptor agonism has moved from hypothesis to high-confidence clinical outcome.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Retatrutide-Clinical-Trials-Explained-Phase-2-to-Phase-3-Outcomes-Endpoints-and-What-Researchers-Should-Track.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-14 16:48:362026-07-20 15:03:14Retatrutide Clinical Trials Explained: Phase 2 to Phase 3 Outcomes, Endpoints, and What Researchers Should Track
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top