Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu
BPC-157 and TB-500: How Researchers Think About Multi-Peptide Tissue-Repair Models

BPC-157 and TB-500: How Researchers Think About Multi-Peptide Tissue-Repair Models

June 10, 2026/0 Comments/by Pure Tested

Fewer than a handful of peptide pairings generate as much discussion in preclinical research circles as BPC-157 and TB-500. The reason is straightforward: these two compounds appear to act on different but overlapping repair pathways, which makes them a natural subject for researchers designing multi-peptide tissue-repair models. Understanding why scientists study them together — and where the evidence actually stands — is essential for anyone comparing single-peptide and stack-based experimental frameworks.
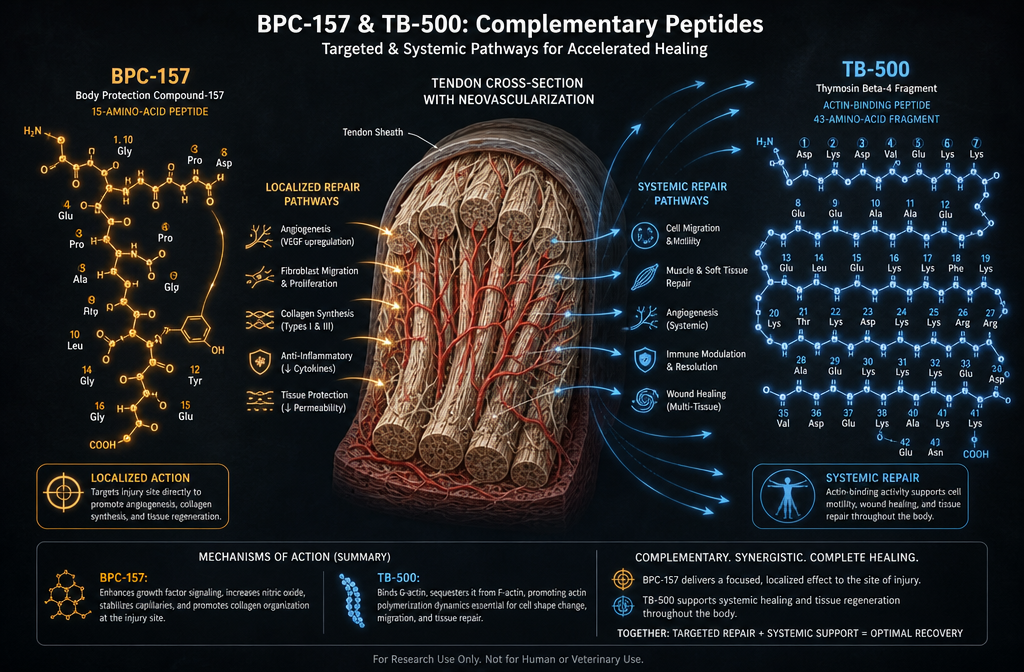
() scientific illustration showing two distinct peptide molecules — one compact 15-amino-acid chain labeled BPC-157 glowing

Key Takeaways

  • BPC-157 targets localized tissue repair through angiogenesis and nitric oxide modulation; TB-500 supports systemic healing via actin regulation and cell migration.
  • When combined in what researchers call the "Wolverine Stack," the two peptides are studied for complementary local and systemic repair coverage.
  • Preclinical animal models show improvements in tensile strength, collagen organization, and recovery time when both peptides are used together.
  • Neither compound holds FDA approval; both are classified as research-only substances and are banned by WADA under the S0 category.
  • Human clinical data remain limited, making rigorous experimental design and verified sourcing critical for any legitimate research program.

Complementary Mechanisms: Why Researchers Pair These Two Peptides

At the core of BPC-157 and TB-500: how researchers think about multi-peptide tissue-repair models is a simple mechanistic logic. The two peptides do not duplicate each other — they fill different roles.

BPC-157 is a 15-amino-acid peptide derived from human gastric juice. Its proposed mechanisms center on:

  • Promoting angiogenesis (new blood vessel formation) at injury sites
  • Modulating nitric oxide signaling to improve local blood flow
  • Upregulating growth factors that support tendon, ligament, and gastrointestinal tissue repair

TB-500, a synthetic fragment of thymosin beta-4, works differently. It is thought to:

  • Regulate actin polymerization, which is essential for cell movement and structural repair
  • Facilitate cell migration toward damaged tissue from distant sites
  • Support recovery in muscle, cardiac, and dermal tissues through systemic distribution

"The mechanistic distinction — localized versus systemic — is precisely why researchers designing multi-peptide models find value in studying these compounds together rather than in isolation."

This complementary profile is why the combination is sometimes called the "Wolverine Stack" in research shorthand. For a broader look at how tissue biology underpins these models, the recovery and tissue biology overview provides useful foundational context.


Preclinical Evidence and Dosing Frameworks in Multi-Peptide Research
Preclinical Evidence and Dosing Frameworks in Multi-Peptide Research

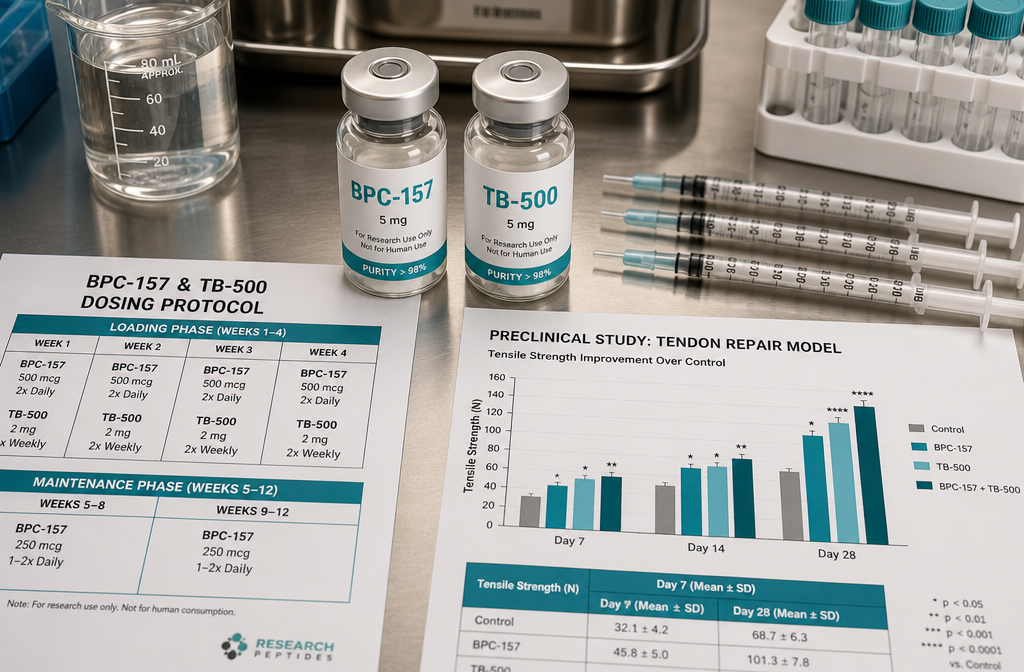
Animal studies form the current backbone of evidence for BPC-157 and TB-500: how researchers think about multi-peptide tissue-repair models. Preclinical data from Achilles tendon injury models, ligament damage studies, and cardiac ischemia/reperfusion experiments consistently show that the combination produces measurable improvements in:

Outcome Measure Observed in Preclinical Models
Tensile strength Increased in tendon repair models
Collagen organization Improved fiber alignment
Recovery timeline Shortened vs. control groups
Cardiac tissue preservation Reduced ischemia-related damage

Researchers working with these compounds typically follow distinct dosing frameworks:

  • BPC-157: 250–500 mcg once or twice daily, administered subcutaneously near the injury site or orally for gastrointestinal applications
  • TB-500: 2–2.5 mg twice weekly during a loading phase, followed by 2 mg weekly for maintenance, administered subcutaneously at any site due to its systemic distribution

For deeper dives into each compound individually, the BPC-157 angiogenesis and tendon research overview and the TB-500 muscle recovery research themes page offer detailed mechanistic breakdowns. The TB-500 cytoskeletal remodeling research article is also directly relevant for understanding actin-related repair pathways.


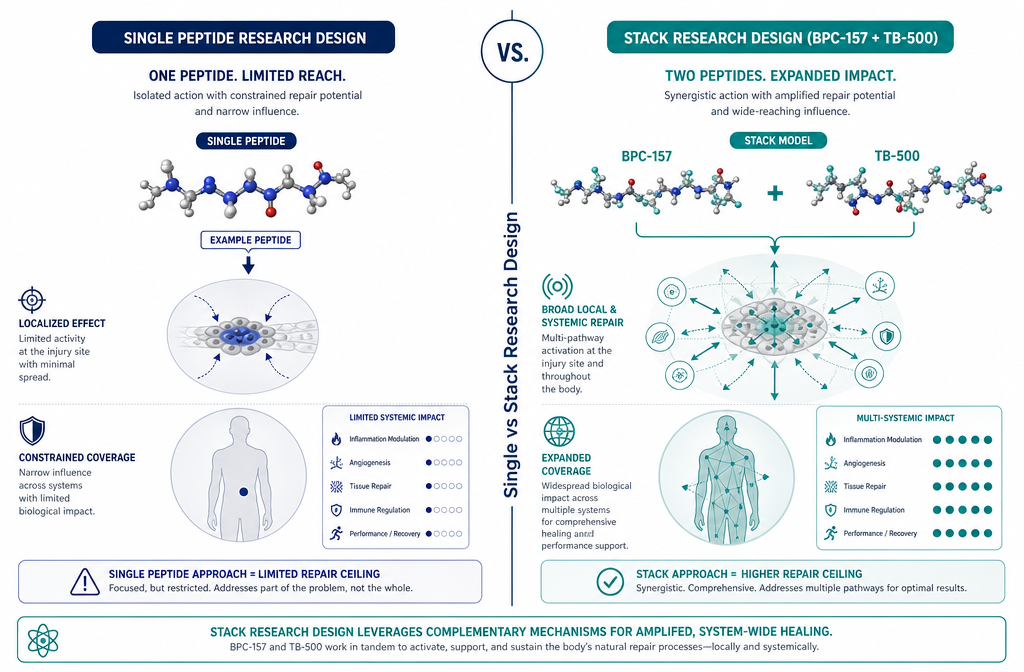
Single-Peptide vs. Stack Models: Where the Evidence Diverges
Single-Peptide vs. Stack Models: Where the Evidence Diverges

The central question for researchers designing experiments around BPC-157 and TB-500: how researchers think about multi-peptide tissue-repair models is whether combined use produces outcomes that neither peptide achieves alone. Preclinical data suggest it does — but with important caveats.

Human clinical data remain scarce. BPC-157 has been examined in only a small number of pilot studies. TB-500 has progressed to Phase 2/3 clinical trials in specific formulations, but comprehensive human data are still absent. This gap between preclinical promise and clinical validation is the defining challenge of the field in 2026.

Researchers should also note two regulatory realities:

  1. Neither BPC-157 nor TB-500 holds FDA approval for therapeutic use. Both are classified as research compounds only.
  2. WADA prohibits both substances under the S0 category (Non-Approved Substances), making them banned in competitive sport contexts.

For researchers interested in how multi-peptide synergy concepts apply to other compound pairings, the synergy of LL-37 and MOTS-c research page offers a useful parallel framework. Those sourcing compounds for legitimate research programs should also review Bachem reference standards and peptide benchmarking to ensure purity verification is part of the experimental design.


Conclusion

The case for studying BPC-157 and TB-500 together rests on a mechanistically coherent rationale: one peptide addresses localized repair, the other supports systemic healing, and preclinical evidence suggests the combination outperforms either agent alone in several tissue models. However, the field is still in early stages. Human data are limited, regulatory status is clear (research-only), and rigorous experimental controls are non-negotiable.

Actionable next steps for researchers:

  • Review the preclinical literature on tendon, ligament, and cardiac repair models before designing any experimental protocol.
  • Establish purity benchmarks using certified reference standards before sourcing either compound.
  • Design experiments with appropriate single-peptide control arms to isolate stack-specific effects.
  • Monitor the regulatory landscape, as both peptides remain unapproved and WADA-prohibited as of 2026.

The multi-peptide tissue-repair model is a compelling research framework — but its value depends entirely on the quality of the science behind it.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/BPC-157-and-TB-500-How-Researchers-Think-About-Multi-Peptide-Tissue-Repair-Models.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-10 13:05:002026-07-20 15:03:34BPC-157 and TB-500: How Researchers Think About Multi-Peptide Tissue-Repair Models
Enclomiphene in Male Endocrine Research: Mechanism vs Clomiphene and Overlaps With Luteinizing Phase Physiology

Enclomiphene in Male Endocrine Research: Mechanism vs Clomiphene and Overlaps With Luteinizing Phase Physiology

June 9, 2026/0 Comments/by Pure Tested

Only one isomer inside a decades-old fertility drug is responsible for raising testosterone in men — and isolating it may change how researchers approach male hypogonadism entirely. That single compound is enclomiphene, and its growing presence in male endocrine research is reshaping how scientists think about the hypothalamic-pituitary-gonadal (HPG) axis.

Research into enclomiphene in male endocrine research: mechanism vs clomiphene and overlaps with luteinizing phase physiology has accelerated in 2026, driven by demand for testosterone-raising strategies that do not suppress fertility. Understanding why enclomiphene works — and how it differs from its parent compound — requires a close look at receptor pharmacology and the fundamental biology of luteinizing hormone (LH) signaling.

Key Takeaways

  • Enclomiphene is the trans-isomer of clomiphene citrate and is solely responsible for its anti-estrogenic, testosterone-stimulating effects in men.
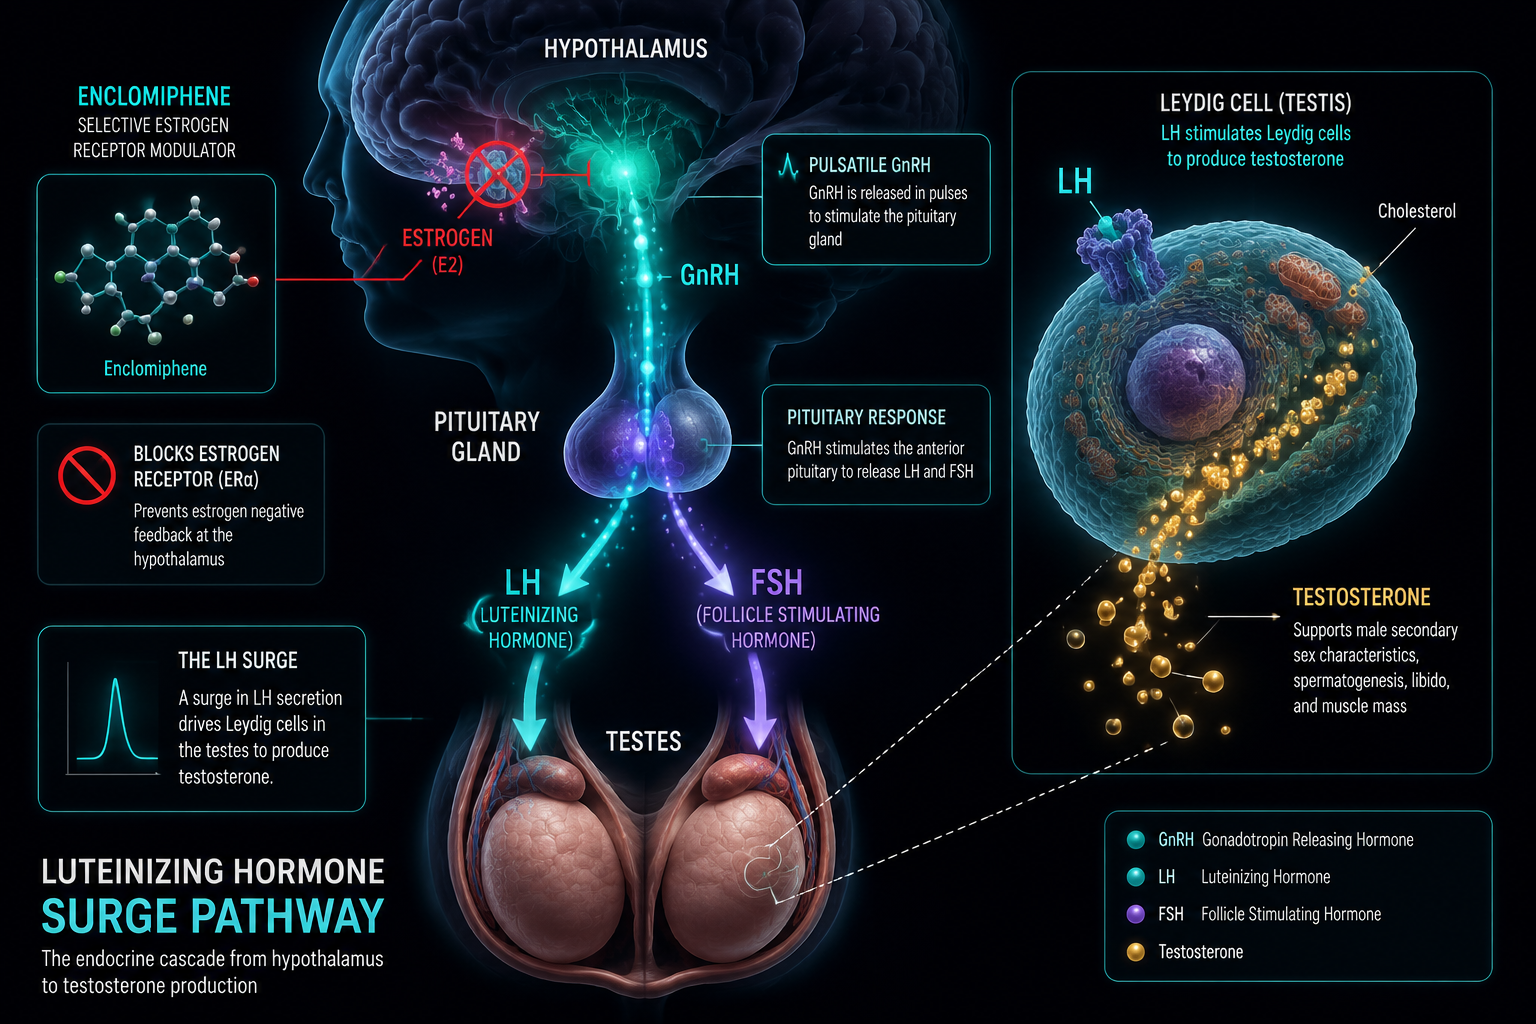
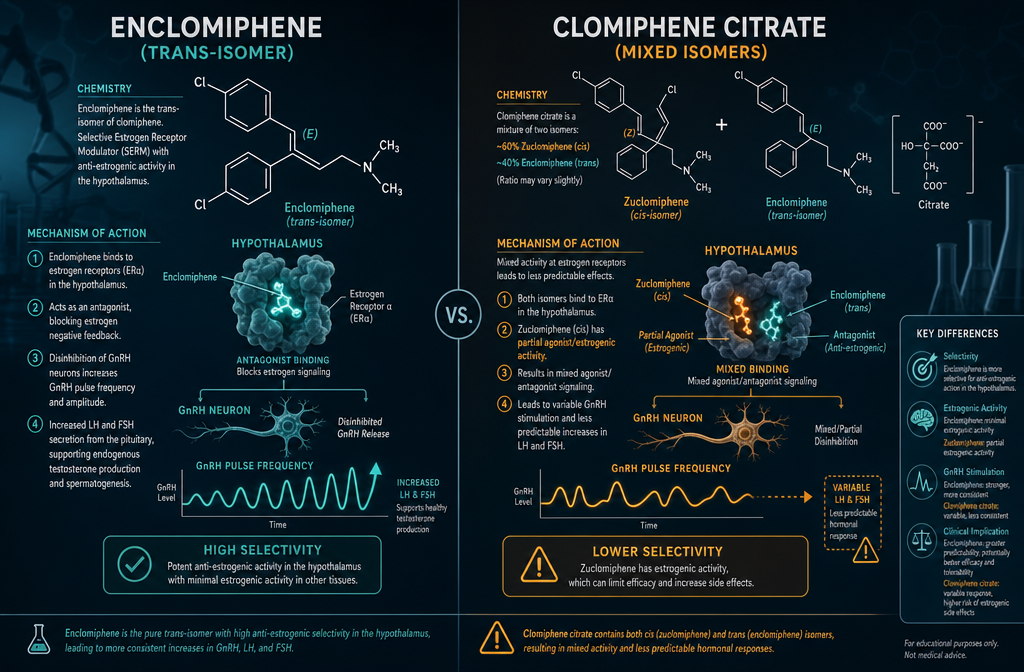
  • It blocks hypothalamic estrogen receptors, increasing GnRH pulsatility and driving LH and FSH release — mirroring the natural luteinizing phase feedback loop.
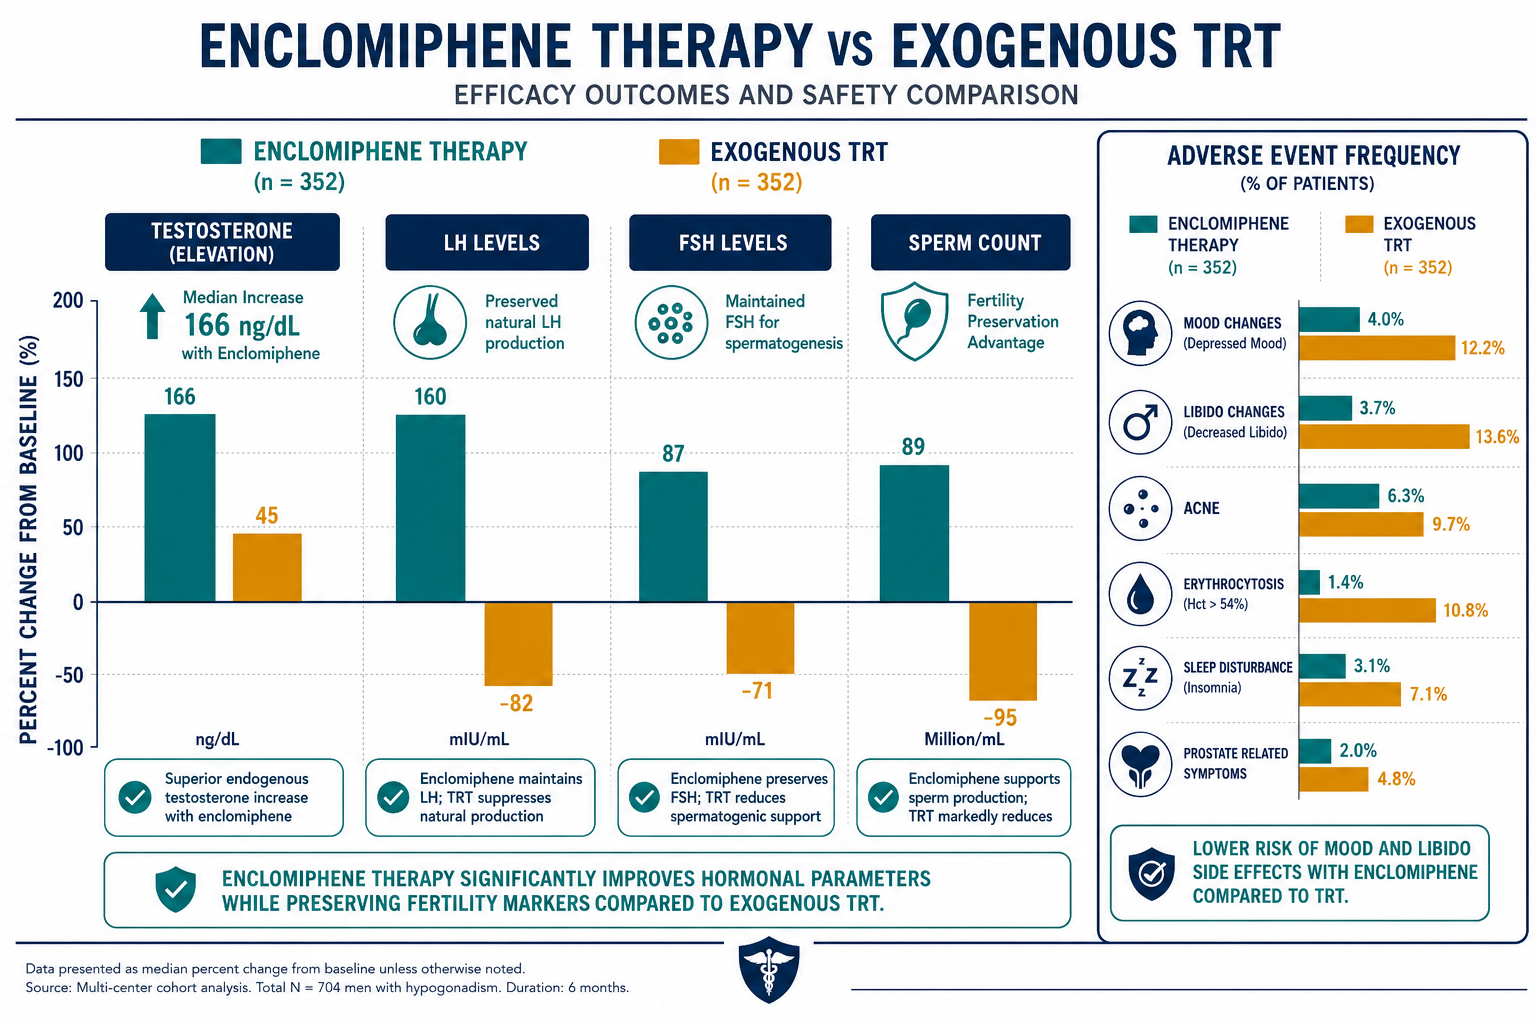
  • Unlike exogenous testosterone replacement therapy (TRT), enclomiphene preserves sperm production and endogenous hormone signaling.
  • Zuclomiphene, the other isomer in clomiphene, carries weak estrogenic activity and a longer half-life, contributing to mood and visual side effects.
  • Clinical data show enclomiphene produces meaningful testosterone increases with a lower adverse-event profile than mixed clomiphene.

Key Takeaways

How Enclomiphene Works: Selective Estrogen Receptor Modulation

Enclomiphene is classified as a selective estrogen receptor modulator (serm). Its primary action occurs at estrogen receptors in the hypothalamus and pituitary gland. Under normal physiology, circulating estradiol binds to these receptors and signals the hypothalamus to reduce gonadotropin-releasing hormone (GnRH) output — a classic negative feedback loop.

Enclomiphene competitively blocks those receptors. With estradiol unable to deliver its suppressive signal, GnRH pulsatility increases. The pituitary responds by secreting more LH and FSH. Elevated LH then stimulates Leydig cells in the testes to synthesize testosterone, while FSH supports spermatogenesis.

Key pharmacokinetic facts:

Parameter Value
Half-life ~10 hours
Time to peak serum concentration 2-3 hours post-ingestion
Steady-state dose 25 mg/day

This rapid clearance is clinically significant. Because enclomiphene leaves the body quickly, its receptor blockade is time-limited and controllable — a meaningful advantage in research settings.


Enclomiphene in Male Endocrine Research: Mechanism vs Clomiphene and Overlaps With Luteinizing Phase Physiology

Enclomiphene in Male Endocrine Research: Mechanism vs Clomiphene and Overlaps With Luteinizing Phase Physiology

The Isomer Problem With Clomiphene Citrate

Clomiphene citrate is not a single compound. It is a 50:50 mixture of two geometric isomers:

  • Enclomiphene (trans-isomer): Blocks estrogen receptors, drives GnRH and LH release, raises testosterone.
  • Zuclomiphene (cis-isomer): Carries weak estrogenic activity, has a much longer half-life, and accumulates in tissue over time.

Zuclomiphene's estrogenic activity and slow elimination are linked to side effects reported with clomiphene use, including mood disturbances, reduced libido, and visual changes. By isolating enclomiphene, researchers remove this confounding variable entirely.

Connection to Luteinizing Phase Physiology

The luteinizing phase in reproductive biology refers to the period surrounding the LH surge — a sharp spike in LH that triggers ovulation in females and, in males, governs tonic testosterone production. In men, LH is released in pulses from the pituitary throughout the day, each pulse prompting Leydig cell testosterone output.

Enclomiphene essentially amplifies this pulsatile system. By lifting estradiol's brake on the hypothalamus, it restores or enhances the natural LH-driven testosterone cascade. This overlap with luteinizing phase physiology is why enclomiphene is particularly relevant for men with secondary hypogonadism — a condition where the testes are functional but the upstream HPG signaling is insufficient.

Researchers studying neuroendocrine and innate immunity interactions will recognize this HPG axis modulation as part of a broader hormonal communication network that extends well beyond reproductive function.


Clinical Evidence and Safety Profile

Clinical Evidence and Safety Profile

A retrospective study of 66 patients found that enclomiphene produced a median testosterone increase of 166 ng/dL with a statistically lower rise in estradiol compared to clomiphene. Adverse effects — including decreased libido, reduced energy, and mood changes — were significantly less frequent with enclomiphene.

Unlike exogenous TRT, which suppresses LH, FSH, and sperm production through negative feedback, enclomiphene maintains or improves sperm counts. This makes it a distinct research focus for hypogonadal men who may wish to preserve fertility.

Researchers exploring metabolic modulation research lines may find enclomiphene's downstream effects on body composition and energy metabolism worth examining alongside testosterone normalization data.

Compounds that modulate the HPG axis often intersect with broader metabolic pathways. For context on related peptide-based research tools, MOTS-c and metabolic flexibility research offers a parallel lens on mitochondrial and hormonal crosstalk.

Enclomiphene vs Clomiphene: Quick Comparison

Feature Enclomiphene Clomiphene Citrate
Isomer composition Trans only Trans + cis (50:50)
Estrogenic activity None Mild (via zuclomiphene)
Half-life ~10 hours Longer (zuclomiphene accumulates)
LH/FSH stimulation Strong Moderate
Fertility preservation Yes Partial
Mood/visual side effects Lower frequency Higher frequency

Researchers also studying neural and arousal pathways may find relevant context in PT-141 neural and metabolic research themes, as central neuroendocrine signaling connects testosterone regulation with broader behavioral physiology.

For those examining body composition outcomes alongside hormonal normalization, TESA body composition research themes and IPA muscle and fat research themes provide complementary data on how hormonal environments shape tissue-level outcomes.


Conclusion

The study of enclomiphene in male endocrine research: mechanism vs clomiphene and overlaps with luteinizing phase physiology clarifies a critical point: not all serms are equal, and isomer composition matters enormously. Enclomiphene's clean receptor blockade at the hypothalamus restores the natural LH-driven testosterone pathway without the estrogenic noise introduced by zuclomiphene.

Actionable next steps for researchers in 2026:

  • Prioritize enclomiphene over mixed clomiphene in male HPG axis models to reduce confounding estrogenic variables.
  • Examine LH pulsatility data alongside testosterone outcomes to map the full luteinizing phase overlap.
  • Investigate enclomiphene's role in secondary hypogonadism models where upstream signaling — not testicular function — is the limiting factor.
  • Cross-reference testosterone normalization data with metabolic and body composition endpoints for a more complete hormonal profile.

As regulatory and clinical interest in enclomiphene grows, its mechanistic clarity makes it a valuable tool for researchers who need precise, reproducible HPG axis modulation without the side-effect profile of its predecessor.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Enclomiphene-in-Male-Endocrine-Research-Mechanism-vs-Clomiphene-and-Overlaps-With-Luteinizing-Phase-Physiology.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-09 13:07:172026-07-20 15:03:34Enclomiphene in Male Endocrine Research: Mechanism vs Clomiphene and Overlaps With Luteinizing Phase Physiology
How to Choose a Peptide Supplier for Research Use Only: Purity, COAs, and Red Flags Explained

How to Choose a Peptide Supplier for Research Use Only: Purity, COAs, and Red Flags Explained

June 9, 2026/0 Comments/by Pure Tested

Roughly 30% of research compounds purchased online fail independent purity verification — a sobering figure for any scientist whose experimental outcomes depend on what is actually inside the vial. Understanding how to choose a peptide supplier for research use only: purity, COAs, and red flags explained is not a bureaucratic exercise; it is the foundation of reproducible science.

Key Takeaways

  • Research-grade peptides should carry a minimum purity of 98% confirmed by HPLC analysis from an independent, accredited laboratory.
  • Every batch needs its own unique Certificate of Analysis (COA) with a matching lot number — generic, reused COAs are a serious red flag.
  • Legitimate COAs include both HPLC chromatograms and mass spectrometry data confirming peptide identity.
  • Suppliers must label products "Research Use Only" and must not make therapeutic or clinical claims.
  • Price, community reputation, and supplier transparency are secondary filters that help narrow down trustworthy vendors.

Key Takeaways

Purity Standards: Why 98% Is the Baseline, Not a Bonus

When evaluating any research peptide vendor, purity is the first non-negotiable metric. Research-grade peptides should achieve a minimum purity of 98% as measured by High-Performance Liquid Chromatography (HPLC). Any product falling below this threshold introduces impurities — truncated sequences, oxidized residues, or synthesis byproducts — that can skew binding assays, cell viability studies, and animal model outcomes in ways that are difficult to detect and nearly impossible to correct retroactively.

HPLC alone, however, is not sufficient. A credible supplier pairs HPLC data with mass spectrometry (LC-MS or MALDI-TOF) to confirm that the molecular weight of the compound matches the theoretical sequence. Together, these two analytical methods answer two distinct questions:

Test What It Confirms
HPLC Purity percentage and absence of major impurities
Mass Spectrometry Correct molecular identity and sequence integrity

For in vivo research models, a third data point becomes critical: endotoxin testing. Bacterial endotoxins — lipopolysaccharides shed from gram-negative bacteria during synthesis — can trigger severe immune responses in animal subjects, completely confounding experimental results. Any supplier serving researchers running in vivo protocols should include endotoxin levels on the COA.

Researchers studying compounds like SS-31 peptides or BPC-157 should specifically verify that purity documentation covers the exact batch received, not a representative sample from a prior production run.


Purity Standards: Why 98% Is the Baseline, Not a Bonus

How to Read a COA: Batch Numbers, Chromatograms, and What Legitimate Documentation Looks Like

A Certificate of Analysis is only as useful as the information it contains. Knowing how to choose a peptide supplier for research use only means knowing how to interrogate this document critically.

Four elements every legitimate COA must include:

  1. Batch or lot number that matches the number printed on the product label — if these do not align, the COA may not apply to the vial in hand.
  2. HPLC chromatogram showing the actual peak profile, not just a reported percentage. A supplier providing only a number without the underlying chromatogram is offering an unverifiable claim.
  3. Mass spectrometry spectrum confirming molecular weight, ideally with the observed versus theoretical mass comparison clearly stated.
  4. Name of the third-party testing laboratory — independent accredited labs carry far more credibility than in-house testing, which cannot be independently audited.

"A COA that cannot be traced to a specific batch and a named independent laboratory is not a certificate of analysis — it is a marketing document."

Generic COAs reused across multiple products or batches are among the most common red flags in the peptide research supply market. Suppliers offering compounds such as Epithalon or Thymosin Alpha-1 should provide batch-specific documentation for every order. Reviewing a supplier's published COA library before purchasing is a practical first step.


How to Read a COA: Batch Numbers, Chromatograms, and What Legitimate Documentation Looks Like

Red Flags, Regulatory Language, and Supplier Transparency

The final layer of due diligence in how to choose a peptide supplier for research use only: purity, COAs, and red flags explained involves evaluating the supplier's conduct, not just their paperwork.

Red flags to watch for:

  • No physical address or verifiable contact information on the website
  • Therapeutic or clinical claims about peptide effects (e.g., "treats," "cures," "prescribed for")
  • Pricing dramatically below market average — underdosed or impure products are the most common explanation
  • Identical COAs across multiple different peptides or batches
  • No visible third-party lab affiliation

What legitimate suppliers do differently:

  • Label every product clearly as "Research Use Only" with no implied human-use endorsement
  • Publish transparent quality control processes and are willing to discuss testing methodology directly
  • Maintain an active, verifiable community reputation through documented reviews and scientific forums

Pricing deserves a direct note: suspiciously low prices are not a value proposition. They are a signal. Peptide synthesis at research-grade purity is resource-intensive. A vendor offering MOTS-c or PT-141 at a fraction of market rate has almost certainly cut corners somewhere in synthesis, purification, or testing.

Regulatory compliance is equally non-negotiable. In 2026, regulatory scrutiny of research peptide vendors continues to increase. Suppliers making health claims or marketing peptides for human use are operating outside compliance boundaries — and purchasing from them exposes researchers to both scientific and legal risk. Reviewing a supplier's full product catalog and FAQ documentation before committing to a vendor relationship is a sound practice.


Conclusion

Choosing a research peptide supplier is a scientific decision, not a shopping decision. The checklist is straightforward: demand 98%+ HPLC-confirmed purity, require batch-specific COAs from named independent laboratories, verify mass spectrometry data, and confirm endotoxin testing for any in vivo application. Walk away from any vendor missing these elements, making therapeutic claims, or offering prices that defy the economics of quality synthesis.

Actionable next steps for 2026:

  • Before ordering, request the COA for the specific batch you will receive and cross-reference the lot number.
  • Verify the named testing laboratory is accredited and independently searchable.
  • Search the supplier's name in scientific community forums and documented review sources.
  • Confirm all product pages carry "Research Use Only" language with no clinical claims.
  • Consult the supplier's FAQ section and documentation resources to assess transparency before purchase.

Rigorous vendor selection is the first experiment in any research protocol — and it deserves the same analytical rigor as every experiment that follows.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/How-to-Choose-a-Peptide-Supplier-for-Research-Use-Only-Purity-COAs-and-Red-Flags-Explained.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-09 13:05:422026-07-20 15:03:35How to Choose a Peptide Supplier for Research Use Only: Purity, COAs, and Red Flags Explained
Tesamorelin, CJC‑1295, and Ipamorelin Stacks: How Researchers Compare Multi‑Peptide Blends to Single‑Peptide Protocols

Tesamorelin, CJC‑1295, and Ipamorelin Stacks: How Researchers Compare Multi‑Peptide Blends to Single‑Peptide Protocols

June 9, 2026/0 Comments/by Pure Tested

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay: 'Peptide Stacks vs Single Protocols: Tesamorelin, CJC-1295 & Ipamorelin' in extra large 72pt white bold sans-serif font with dark semi-transparent overlay box, centered upper-third composition. Background shows a high-resolution laboratory research setting with glass vials, molecular structure diagrams, and soft blue lighting with white accents. Color palette: deep navy blue, crisp white, and teal highlights. Magazine cover aesthetic, editorial quality, high contrast.","content":["Detailed landscape format (1536×1024) scientific illustration showing three distinct peptide molecular structures labeled Tesamorelin, CJC-1295, and Ipamorelin arranged side by side with connecting arrows indicating GH-axis pathway activation. Background features a stylized pituitary gland diagram with GH pulse waveforms. Color scheme: clinical white, deep blue, and amber highlights. Infographic style with clean sans-serif annotations, research laboratory aesthetic, high detail.","Aerial top-down view of a researcher's desk showing a comparison chart contrasting single-peptide protocol data versus multi-peptide blend data, with bar graphs showing 17% VAT reduction figures, regulatory status badges (FDA-approved vs research chemical), and dose-sparing calculation notes on a digital tablet. Scattered research papers, a calculator, and peptide vials visible. Color palette: warm white desk surface, navy data graphics, green and red status indicators. Editorial research aesthetic.","Close-up wide-angle shot of a laboratory bench with precisely measured peptide vials arranged in a row showing dose-sparing blend formulations, a digital scale, and a research protocol notebook open to a page titled Multi-Peptide Stack Design Considerations. Soft overhead lighting with clinical blue-white tones. One vial labeled with a triple-blend formulation tag. Background shows blurred centrifuge equipment. Color scheme: sterile white, steel grey, and accent blue. High-resolution editorial quality."]

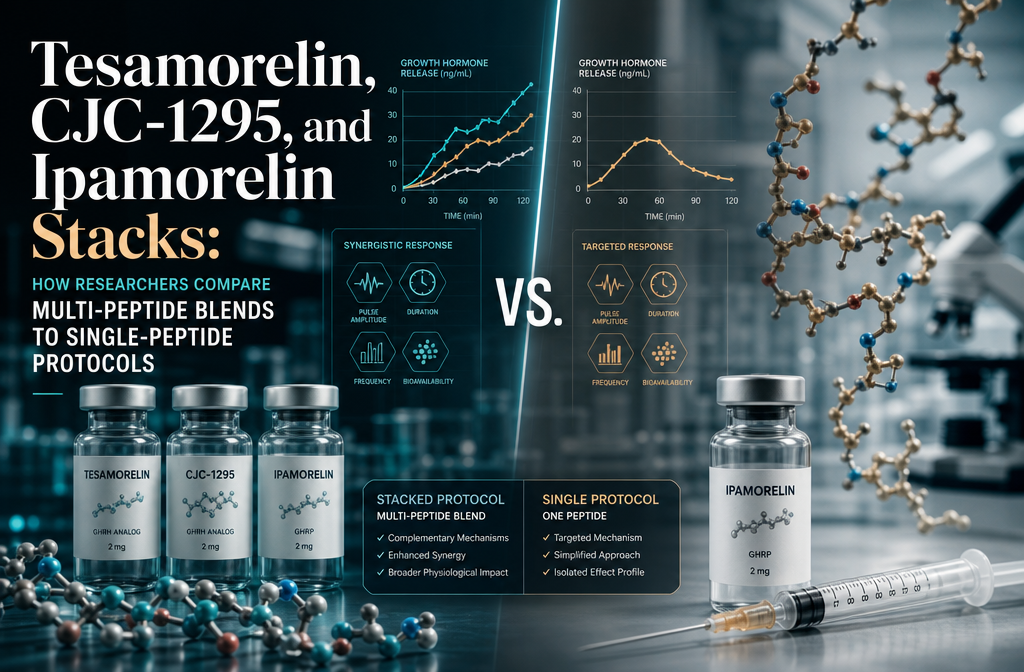
Professional landscape hero image () with : "Tesamorelin, CJC-1295, and Ipamorelin Stacks: How Researchers Compare

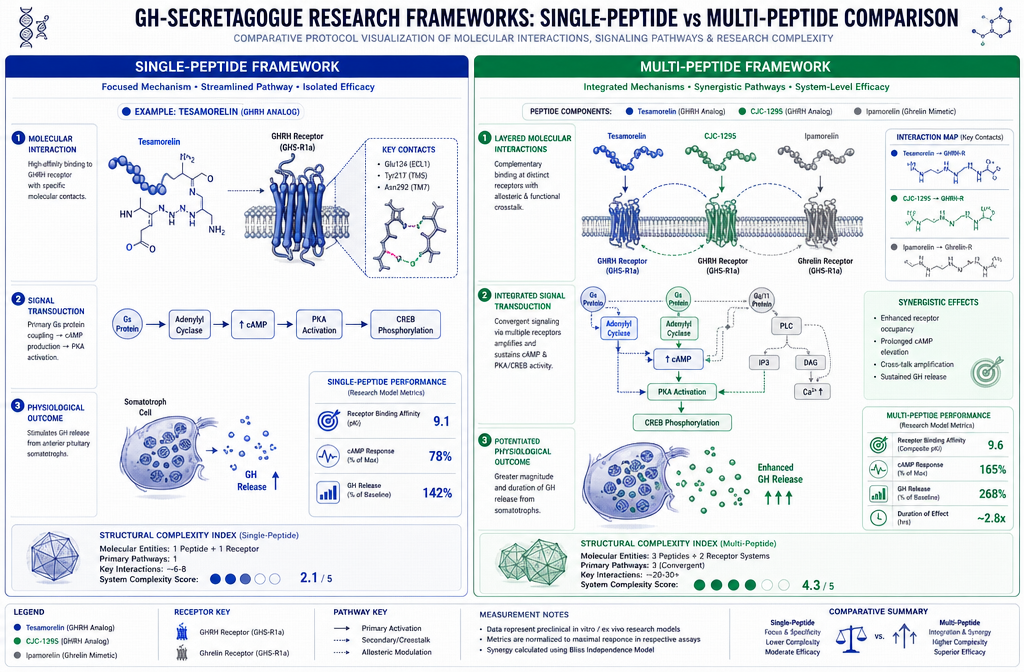
Only one peptide in the GH-secretagogue class has cleared the bar of FDA approval and multiple randomized controlled trials — and it is almost always studied alone. That single fact defines the central tension researchers face when evaluating Tesamorelin, CJC-1295, and Ipamorelin stacks: How researchers compare multi-peptide blends to single-peptide protocols reveals a sharp divide between what is clinically proven and what is mechanistically plausible.

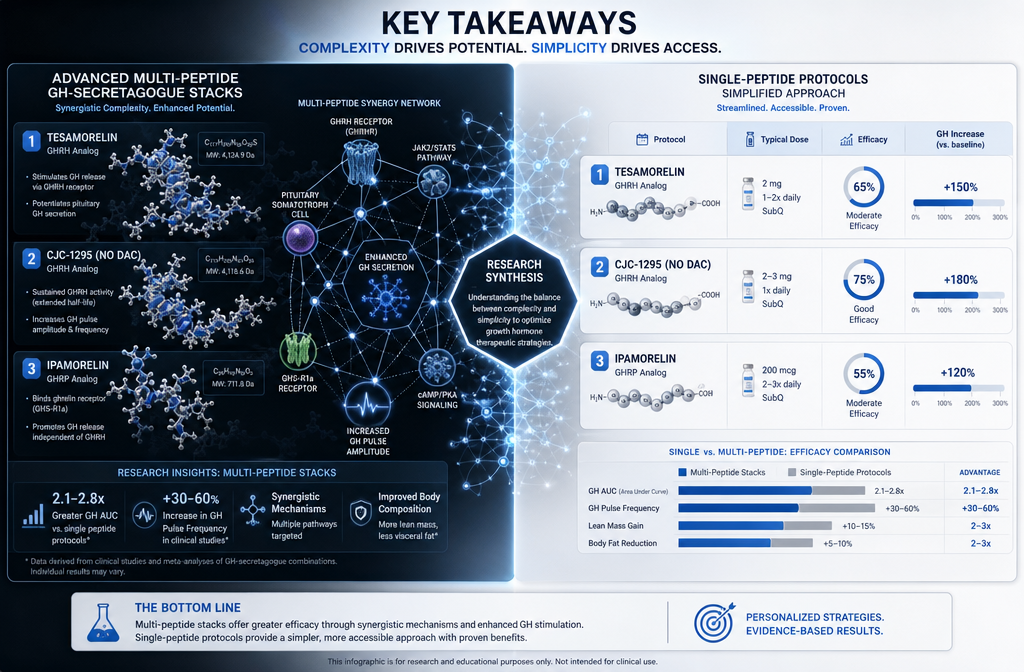
Key Takeaways section infographic: Split-screen scientific visualization comparing multi-peptide GH-secretagogue stacks

Key Takeaways

  • Tesamorelin monotherapy has robust RCT evidence showing roughly 17% visceral adipose tissue (VAT) reduction at six months; no equivalent data exist for CJC-1295 or Ipamorelin stacks.
  • CJC-1295 + Ipamorelin combinations sit in the lowest evidence tier for fat loss, classified as mechanistically plausible but clinically under-proven.
  • Triple-blend stacks typically use lower individual doses than standalone protocols, reflecting a dose-sparing research strategy.
  • Regulatory status differs sharply: tesa is FDA-approved for a specific indication; triple-peptide blends are research chemicals not approved for human use.
  • Researchers choosing between protocols should match the peptide to the research question, not assume that more peptides equal better outcomes.

Understanding the Evidence Gap in GH-Secretagogue Research

The GH axis can be stimulated through two distinct receptor pathways: GHRH receptors (targeted by tesa and CJC-1295) and ghrelin/GHS receptors (targeted by ipamorelin). On paper, combining both pathways makes sense — each amplifies GH pulse amplitude through a different mechanism, and preclinical data support synergistic GH release.

The problem is that synergistic GH release is a surrogate marker, not a clinical outcome. Tesamorelin's evidence base is built on hard endpoints. Pooled data from multiple randomized trials in patients with metabolic syndrome show approximately 17.2% VAT reduction at six months alongside meaningful improvements in HbA1c. These results come from tesa used as a monotherapy, not as part of a stack.

CJC-1295 and ipamorelin have no equivalent VAT-specific RCT data. Their reputation for supporting fat loss, lean mass, recovery, and sleep quality rests largely on:

  • Surrogate biomarkers (IGF-1 elevation, GH pulse data)
  • Small or open-label studies
  • Extrapolation from tesa's mechanism
  • Accumulated clinical experience rather than controlled outcomes

For researchers designing protocols, this distinction is not a minor detail — it determines what conclusions can legitimately be drawn from any experiment.


How Researchers Compare Multi-Peptide Blends to Single-Peptide Protocols: Regulatory and Dosing Frameworks

How Researchers Compare Multi-Peptide Blends to Single-Peptide Protocols: Regulatory and Dosing Frameworks

Regulatory status shapes research design as much as pharmacology does. Tesamorelin carries FDA approval for HIV-associated lipodystrophy, which means its dosing, monitoring parameters, and safety profile are well-characterized in published literature. Researchers using it off-label for visceral fat or metabolic endpoints have a defined framework to work within.

Triple-peptide blends — such as the tesa + CJC-1295 + ipamorelin 12mg blend — are explicitly classified as research chemicals not approved for human use. This status places them in a different methodological category. Researchers working with these compounds in preclinical or experimental models must account for the absence of standardized clinical dosing guidance.

When comparing the two approaches, a useful framework is the evidence tier system:

Protocol Type Evidence Tier Key Data Source
Tesamorelin monotherapy High Multiple RCTs, meta-analyses
CJC-1295 + Ipamorelin stack Low Surrogate markers, case series
Tesamorelin + CJC-1295 + Ipamorelin triple blend Lowest Preclinical, mechanistic only

Researchers exploring tesa vs ipamorelin as separate protocols will find that tesa is the evidence-based choice for visceral fat specifically, while ipamorelin-containing stacks are positioned more toward generalized recovery and lean-mass support — a distinction that should inform how any study is designed and how results are interpreted.


Practical Considerations When Designing Multi-Peptide GH Stack Protocols

Practical Considerations When Designing Multi-Peptide GH Stack Protocols

One consistent feature of triple-blend formulations is dose-sparing. Experimental profiles for the tesa + CJC-1295 + ipamorelin combination typically describe each component dosed below its usual standalone level — for example, tesa at 500–1,000 mcg alongside CJC-1295 and ipamorelin each at 100–200 mcg per administration. The rationale is multi-pathway stimulation without proportionally increasing total peptide load.

Researchers considering peptide blend research should weigh several practical factors:

  • Research question specificity: If the target endpoint is visceral fat reduction, single-peptide tesa protocols have validated measurement tools and outcome benchmarks. Multi-peptide blends lack these reference points.
  • Confounding variables: Stacking multiple peptides makes it harder to attribute any observed effect to a specific compound. Single-peptide protocols offer cleaner data.
  • Dose-response clarity: Established tesa dosage guidance exists in the literature; equivalent guidance for triple blends does not.
  • Purity verification: Any multi-peptide blend used in research should come with third-party testing documentation. Reviewing quality testing protocols before sourcing is a critical step.

For researchers interested in broader GH-axis research design, the GH axis product line overview provides useful context on how different secretagogues fit within a structured research framework. Those exploring adjacent peptide categories may also find value in reviewing BPC-157 core peptides documentation for comparison on how single-peptide evidence builds over time.


Conclusion

The comparison between Tesamorelin, CJC-1295, and Ipamorelin stacks and single-peptide protocols ultimately comes down to matching the tool to the task. Tesamorelin monotherapy remains the gold standard for visceral fat research, backed by rigorous clinical trial data. CJC-1295 and ipamorelin combinations offer mechanistic appeal and broader GH-axis stimulation, but researchers must work with the understanding that combination data are thin and clinical outcomes are largely unproven.

Actionable next steps for researchers in 2026:

  1. Define the primary endpoint before selecting a protocol — visceral fat reduction favors tesa alone; recovery and lean-mass models may justify a stack design.
  2. Use single-peptide runs first to establish baseline response data before introducing multi-peptide complexity.
  3. Source only third-party tested compounds and document purity for every experimental batch.
  4. Treat any triple-blend result as hypothesis-generating, not confirmatory, until controlled studies exist.

The gap between mechanistic plausibility and clinical proof is where most peptide stack research currently lives. Acknowledging that gap is the first step toward designing studies that actually close it.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Tesamorelin-CJC‑1295-and-Ipamorelin-Stacks-How-Researchers-Compare-Multi‑Peptide-Blends-to-Single‑Peptide-Protocols.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-09 13:05:282026-07-20 15:03:36Tesamorelin, CJC‑1295, and Ipamorelin Stacks: How Researchers Compare Multi‑Peptide Blends to Single‑Peptide Protocols
Selank vs Semax vs PT-141: A Research-Only Guide to Distinct Neuropeptide Mechanisms, Delivery Routes, and Use Cases

Selank vs Semax vs PT-141: A Research-Only Guide to Distinct Neuropeptide Mechanisms, Delivery Routes, and Use Cases

June 9, 2026/0 Comments/by Pure Tested

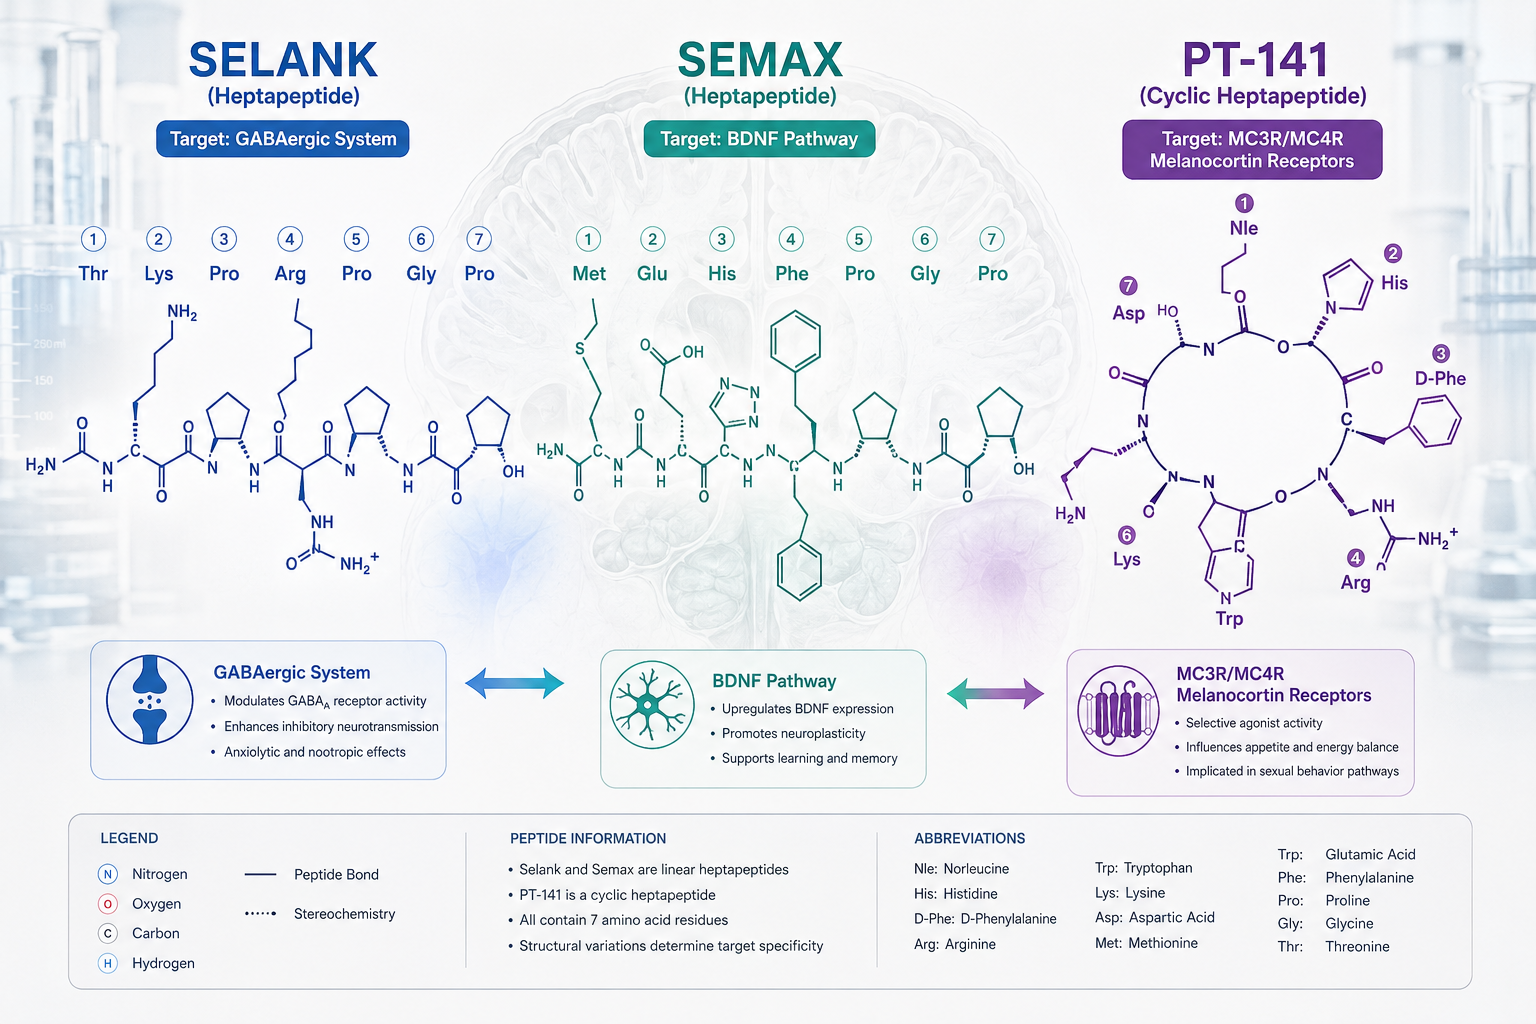
Three synthetic heptapeptides. Three completely different receptor targets. Three delivery strategies that reflect fundamentally different pharmacological goals. Researchers who treat Selank, Semax, and PT-141 as interchangeable nootropic compounds are missing the point entirely — and potentially compromising experimental design in the process.

This guide to Selank vs Semax vs PT-141: A Research-Only Guide to Distinct Neuropeptide Mechanisms, Delivery Routes, and Use Cases breaks down what actually separates these compounds at the mechanistic level, where each one is delivered and why, and which research contexts each one fits.

All three compounds are for research purposes only. None should be used for human self-administration outside of approved clinical settings.


Key Takeaways

  • Selank targets the GABAergic system for anxiolytic effects without sedation; Semax modulates BDNF and monoamine pathways for cognitive enhancement.
  • PT-141 (bremelanotide) acts on central melanocortin receptors MC3R and MC4R — a mechanism entirely unrelated to the other two peptides.
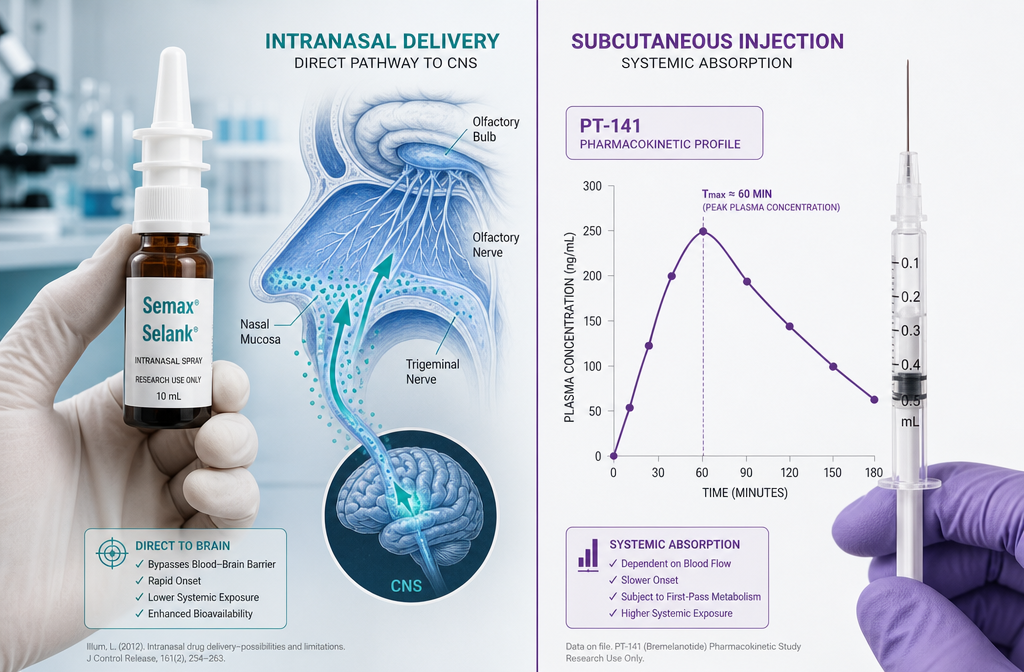
  • Selank and Semax are primarily delivered intranasally; PT-141 is delivered via subcutaneous injection.
  • PT-141 received FDA approval in 2019 for HSDD in premenopausal women; Selank and Semax remain unapproved by the FDA.
  • Choosing the right peptide for a given research model requires understanding receptor specificity, not just general "neuropeptide" classification.

Key Takeaways

Mechanisms: What Each Peptide Actually Does

Understanding this research-only guide to distinct neuropeptide mechanisms starts at the receptor level.

Selank: GABAergic Modulation and Anxiolytic Signaling

Selank is a synthetic analog of the endogenous tetrapeptide tuftsin. Its primary mechanism involves modulating gene expression within the GABAergic system — the same neurotransmitter network targeted by benzodiazepines, but without the sedation or dependence risk associated with those drugs. Research models using Selank focus on anxiety reduction, stress response, and immune-adjacent signaling. For researchers studying the Selank side effects profile, the GABAergic mechanism is central to interpreting observed outcomes.

Semax: BDNF Upregulation and Monoamine Influence

Semax works differently. It is believed to enhance cognitive function by upregulating brain-derived neurotrophic factor (BDNF) and influencing dopaminergic and serotonergic systems. This makes Semax relevant to research on neuroplasticity, attention, and neuroprotection rather than anxiety. The two peptides are frequently compared, but their mechanisms are distinct enough that stacking them in a single model requires careful justification.

PT-141: Central Melanocortin Pathway

PT-141 (bremelanotide) operates through an entirely different system. As a synthetic cyclic heptapeptide, it acts as a melanocortin receptor agonist — specifically targeting MC3R and MC4R in the central nervous system. This distinguishes it sharply from PDE5 inhibitors, which work peripherally. PT-141 enhances sexual desire and arousal through central CNS signaling, not vasodilation. Researchers can explore the PT-141 research context and quality controls for sourcing and experimental design guidance.


Delivery Routes: Why Administration Method Matters

Delivery Routes: Why Administration Method Matters

Delivery route is not a minor detail — it directly affects bioavailability, onset time, and CNS penetration. This section of the Selank vs Semax vs PT-141 guide is where researchers often make consequential decisions.

Intranasal Delivery: Selank and Semax

Both Selank and Semax are administered intranasally in research settings. The nasal mucosa offers rich vascularization and direct neural connections to the CNS via the olfactory pathway. This allows for rapid onset and relatively efficient CNS delivery without requiring injection. The intranasal route is also practical for repeated-dosing protocols.

Peptide Primary Delivery CNS Target Onset
Selank Intranasal GABAergic system Rapid
Semax Intranasal BDNF / Dopamine / Serotonin Rapid
PT-141 Subcutaneous injection MC3R / MC4R ~60 min

Subcutaneous Injection: PT-141

PT-141 follows a different path. The FDA-approved route is subcutaneous injection at 1.75 mg as needed. Following injection, peak plasma concentrations are reached approximately 60 minutes post-administration, with effects lasting 6 to 12 hours. Intranasal PT-141 was explored in early research but showed variable absorption and lower bioavailability, leading to its exclusion from the approved protocol.

Researchers comparing peptide delivery strategies may also find value in reviewing BPC-157 nasal spray and capsule evidence as a parallel case study in route-dependent outcomes.


Research Use Cases and Regulatory Status

Research Use Cases and Regulatory Status

Where Each Peptide Fits in Preclinical Research

Selank is best suited for models examining anxiety, stress resilience, and immune modulation. Its clean anxiolytic profile — without sedation — makes it useful in behavioral paradigms where motor function must remain intact.

Semax fits cognitive enhancement, neuroprotection, and neuroplasticity research. Its BDNF-modulating properties make it relevant in models of neurodegeneration or cognitive decline.

PT-141 belongs in research focused on sexual dysfunction, melanocortin signaling, or CNS-mediated arousal pathways. Its 2019 FDA approval for hypoactive sexual desire disorder (HSDD) in premenopausal women — based on two Phase III trials with 1,247 participants — gives it the strongest clinical validation of the three. Common side effects observed in trials included nausea (approximately 40% of participants), flushing, and headache.

Researchers building multi-peptide protocols may also want to examine how other neuropeptides interact with overlapping systems. The IPA-Sermorelin stack research overview and peptide supplier comparison guide offer useful context for sourcing decisions and protocol design.

Regulatory Landscape in 2026

As of 2026, Semax and Selank remain unapproved by the FDA for any medical use in the United States. They are available for research purposes only. PT-141 holds FDA approval under the brand name Vyleesi, though research-grade material is subject to different handling and documentation standards. Researchers should always verify certificates of analysis — the COA verification resource provides guidance on what to look for.

For those exploring adjacent peptide categories, GHK-Cu copper peptide sourcing guidance and AOD-9604 research method notes illustrate how traceability standards apply across different peptide classes.


Conclusion

The comparison at the heart of Selank vs Semax vs PT-141: A Research-Only Guide to Distinct Neuropeptide Mechanisms, Delivery Routes, and Use Cases reveals three peptides with almost nothing in common beyond their heptapeptide structure. Selank calms through GABAergic modulation. Semax stimulates cognitive pathways via BDNF and monoamines. PT-141 activates melanocortin receptors to influence central arousal signaling.

Actionable next steps for researchers:

  • Match peptide selection to the specific receptor system under investigation — do not group these compounds by structural similarity alone.
  • Account for delivery route when designing dosing intervals and bioavailability assumptions.
  • Verify regulatory status and obtain certificates of analysis before initiating any research protocol.
  • Review published clinical data on PT-141 as a benchmark for what rigorous peptide trial design looks like, then apply those standards to Selank and Semax research where Western-accessible data remains limited.

Precision in peptide research begins with precision in compound selection.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Selank-vs-Semax-vs-PT-141-A-Research-Only-Guide-to-Distinct-Neuropeptide-Mechanisms-Delivery-Routes-and-Use-Cases.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-09 13:05:202026-07-20 15:03:36Selank vs Semax vs PT-141: A Research-Only Guide to Distinct Neuropeptide Mechanisms, Delivery Routes, and Use Cases
What Is GLP-3 Retatrutide? Triple-Agonist Biology, Receptor Targets, and Why It Is Different From GLP-1

What Is GLP-3 Retatrutide? Triple-Agonist Biology, Receptor Targets, and Why It Is Different From GLP-1

June 9, 2026/0 Comments/by Pure Tested

Forty-five percent of participants in a Phase 3 clinical trial lost at least 30% of their body weight — a result once reserved for bariatric surgery. That single data point from the TRIUMPH-1 trial has made retatrutide one of the most closely watched compounds in metabolic medicine today. Understanding what is GLP-3 retatrutide, its triple-agonist biology, receptor targets, and why it is different from GLP-1 drugs already on the market is the essential first step for any researcher or clinician tracking this space.

Key Takeaways

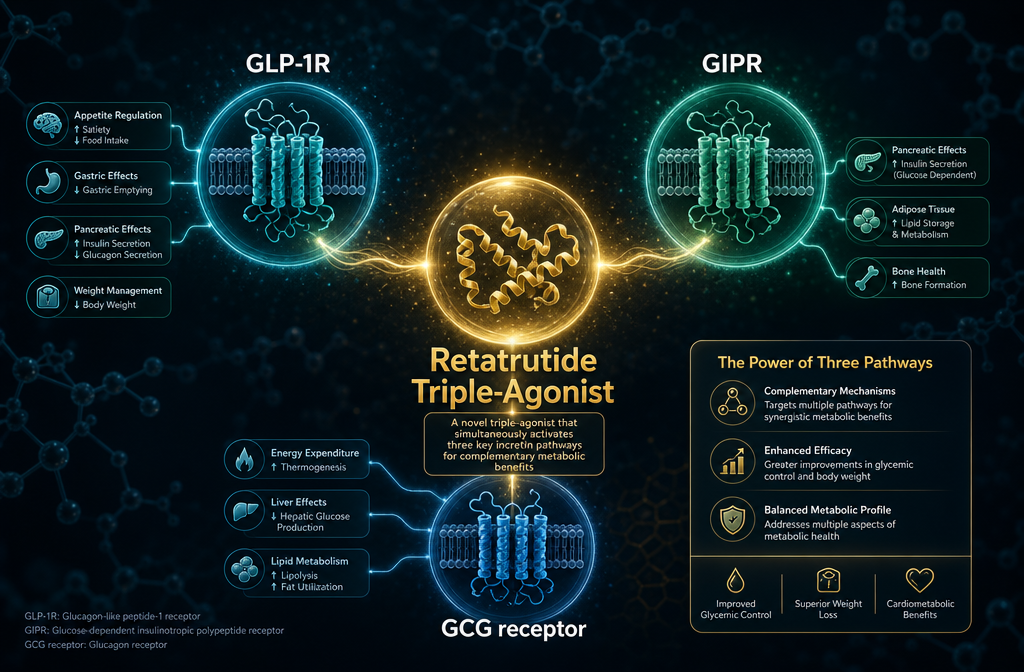
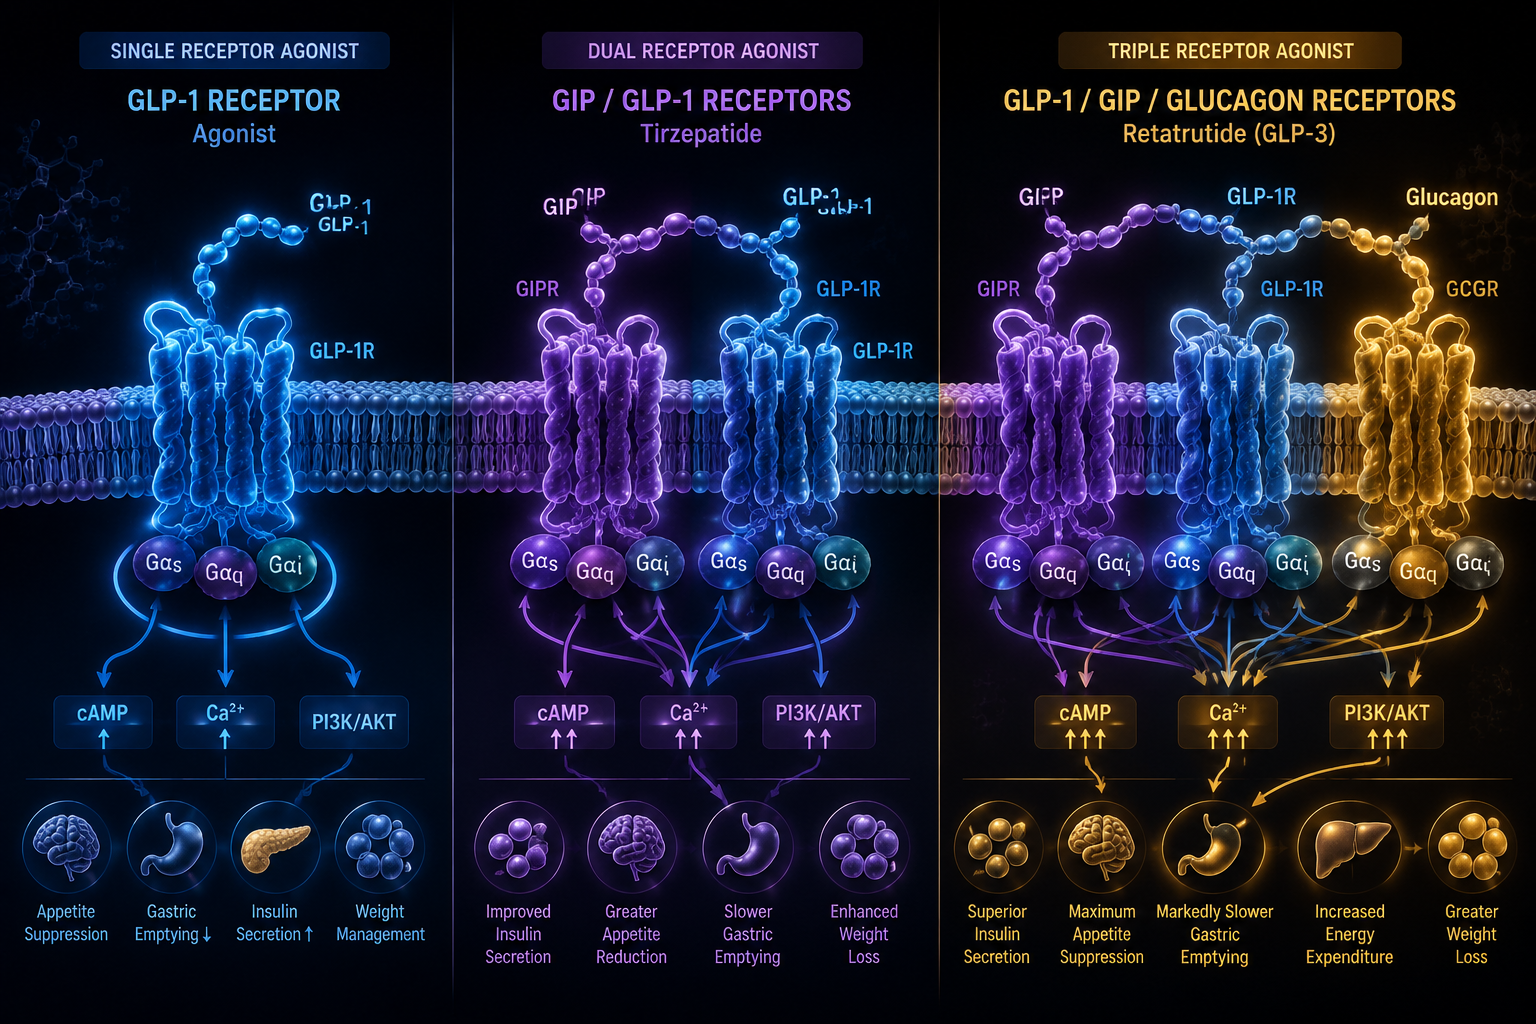
  • Retatrutide simultaneously activates three hormone receptors: GLP-1R, GIPR, and the glucagon receptor (GCG-R).
  • The informal label "GLP-3" is not a scientific hormone classification — it is shorthand for the compound's triple-receptor profile.
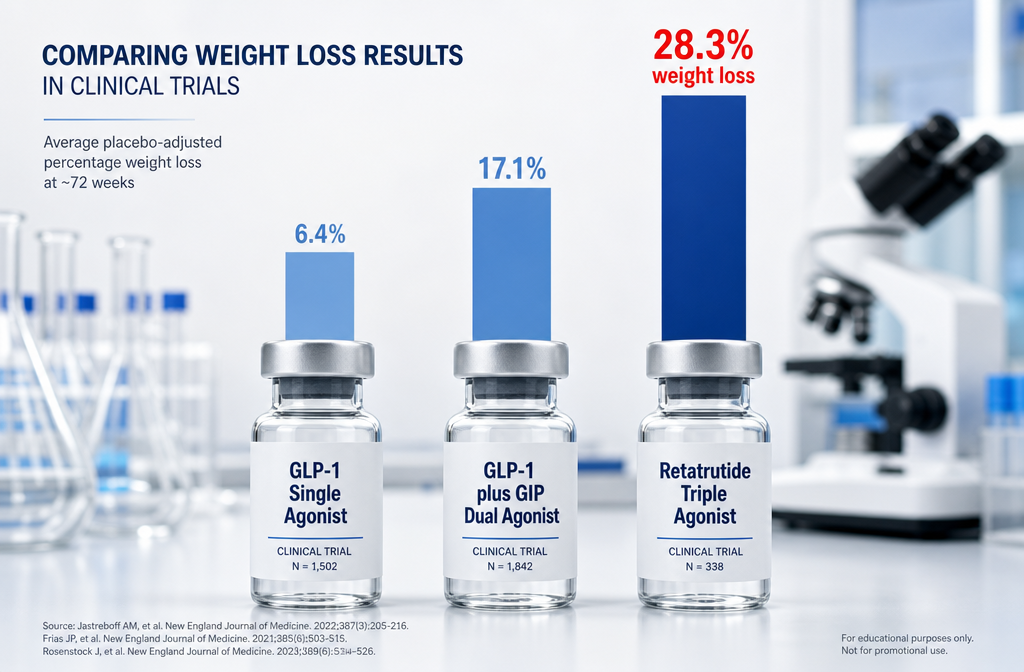
  • In the TRIUMPH-1 Phase 3 trial, participants on 12 mg weekly lost an average of 28.3% of body weight over 80 weeks.
  • Retatrutide outperforms single-agonist (semaglutide) and dual-agonist (tirzepatide) therapies in early head-to-head comparisons.
  • As of 2026, retatrutide has not received FDA approval and remains in Phase 3 development under Eli Lilly.

Key Takeaways

The Triple-Agonist Biology Behind Retatrutide

Retatrutide is a synthetic peptide engineered to bind and activate three distinct incretin and metabolic hormone receptors at the same time. Each receptor plays a separate but complementary role in energy regulation.

Receptor Primary Role Contribution to Retatrutide's Effect
GLP-1R (Glucagon-Like Peptide-1) Insulin secretion, appetite suppression Reduces hunger, slows gastric emptying
GIPR (Glucose-Dependent Insulinotropic Polypeptide) Insulin amplification, fat metabolism Enhances insulin response, supports fat tissue signaling
GCG-R (Glucagon Receptor) Energy expenditure, hepatic glucose output Increases calorie burn, reduces liver fat

This simultaneous three-receptor engagement is what separates retatrutide from every approved obesity drug on the market. The glucagon receptor component is particularly significant: glucagon typically raises blood sugar, but when its receptor is activated alongside GLP-1R and GIPR, the net effect shifts toward increased thermogenesis and fat oxidation rather than hyperglycemia.

Researchers exploring the GLP-1 generations overview will recognize this as a logical progression from first-generation single-agonist molecules toward increasingly complex multi-receptor strategies.

Why the "GLP-3" Label Is Informal — and What It Actually Means

The term "GLP-3" does not refer to a real hormone. No such molecule exists in human physiology. The label emerged informally to describe retatrutide's position as the third generation of GLP-based obesity therapies:

  • Generation 1: GLP-1 single agonists (e.g., semaglutide / Wegovy)
  • Generation 2: GLP-1 + GIP dual agonists (e.g., tirzepatide / Zepbound)
  • Generation 3: GLP-1 + GIP + Glucagon triple agonists (retatrutide)

The correct scientific description is triple hormone receptor agonist. Researchers browsing retatrutide research and catalog resources or the GLP-1 Reta product tag will encounter both terms, but the informal "GLP-3" label should always be understood as generational shorthand rather than pharmacological classification.

Why the "GLP-3" Label Is Informal — and What It Actually Means

How Retatrutide Differs From GLP-1 Drugs: Receptor Targets and Clinical Outcomes

This is the core question for anyone asking what is GLP-3 retatrutide and why it is different from GLP-1. The differences operate on two levels: mechanistic and clinical.

Mechanistically, semaglutide targets only GLP-1R. Tirzepatide adds GIPR. Retatrutide adds the glucagon receptor on top of both. That third receptor drives a meaningful increase in resting energy expenditure — the body burns more calories even at rest — which neither of the earlier drugs can replicate.

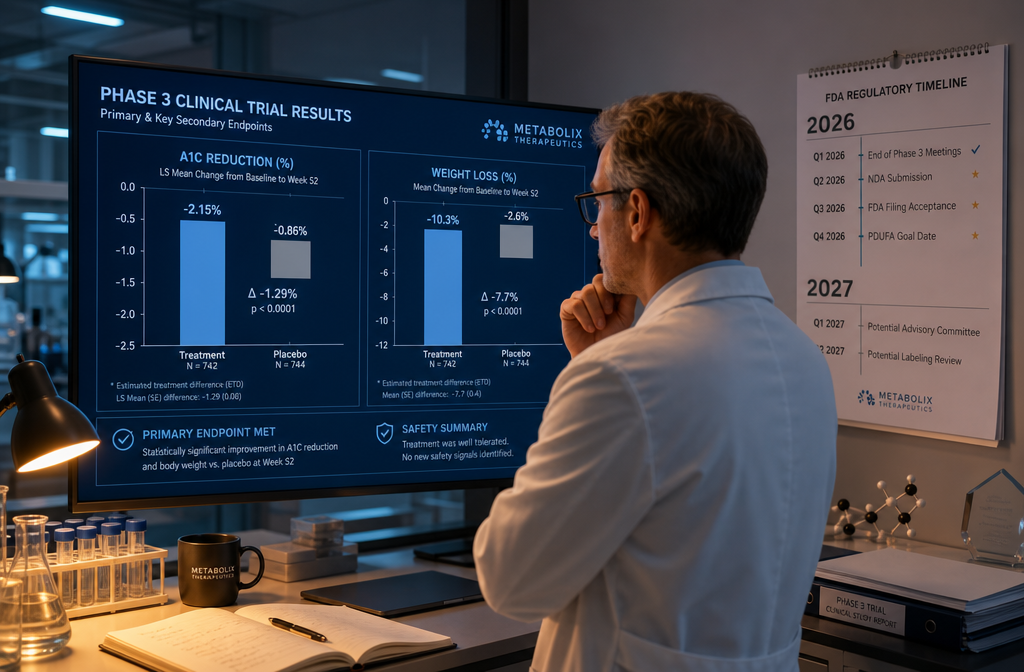
Clinically, the TRIUMPH-1 Phase 3 trial reported an average weight loss of 28.3% (approximately 70.3 pounds) over 80 weeks at the 12 mg weekly dose. By comparison, semaglutide typically produces roughly 15% weight loss, and tirzepatide reaches approximately 20-22%. Retatrutide also demonstrated an A1C reduction of up to 2.0% over 40 weeks in participants with type 2 diabetes, suggesting strong glycemic benefit beyond weight loss alone.

"Retatrutide's glucagon receptor component is the differentiating factor — it converts what would otherwise be a pure appetite-suppression strategy into a genuine energy-expenditure intervention."

Side effects remain consistent with the incretin drug class: nausea, diarrhea, constipation, and vomiting, all dose-dependent and generally manageable. Those interested in how metabolic peptides interact with energy systems may also find value in reviewing mitochondrial longevity research and AOD9604 metabolic research for broader context.

For researchers sourcing compounds for study, reviewing lab-tested peptide standards and certificate of analysis documentation ensures quality benchmarks are met before any research protocol begins.

As of 2026, retatrutide is not FDA-approved. Eli Lilly anticipates filing for approval in 2026-2027, with potential market availability by 2027 or 2028. Those planning research timelines can consult the GLP-3 research planning and catalog navigation guide for sourcing and protocol considerations.

How Retatrutide Differs From GLP-1 Drugs: Receptor Targets and Clinical Outcomes

Conclusion

Retatrutide represents a genuine structural advance over existing GLP-1 therapies. Its triple-agonist biology — engaging GLP-1R, GIPR, and the glucagon receptor simultaneously — produces weight loss outcomes that approach bariatric surgery benchmarks and glycemic improvements that matter for type 2 diabetes management. The informal "GLP-3" label is a useful shorthand, but researchers should understand it as a generational marker, not a hormone designation.

Actionable next steps for researchers in 2026:

  • Review the TRIUMPH-1 Phase 3 trial data in detail to understand dose-response relationships.
  • Compare retatrutide's receptor profile against tirzepatide using the GLP-1 peptide generational research overview.
  • Verify compound purity standards before initiating any research protocol by consulting available COA documentation.
  • Monitor FDA filing timelines, currently projected for 2026-2027, to align research planning accordingly.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/What-Is-GLP-3-Retatrutide-Triple-Agonist-Biology-Receptor-Targets-and-Why-It-Is-Different-From-GLP-1.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-09 13:05:142026-07-20 15:03:37What Is GLP-3 Retatrutide? Triple-Agonist Biology, Receptor Targets, and Why It Is Different From GLP-1
Best Research Peptides for Tissue Repair: Comparing BPC‑157, TB‑500, GHK‑Cu, and Glow/Klow Blends for In‑Vitro and Animal Models

Best Research Peptides for Tissue Repair: Comparing BPC‑157, TB‑500, GHK‑Cu, and Glow/Klow Blends for In‑Vitro and Animal Models

June 8, 2026/0 Comments/by Pure Tested

Fewer than 30 human subjects have been enrolled across all published pilot studies on BPC‑157 combined — yet preclinical data on this and related peptides continues to accelerate at a striking pace. For researchers selecting compounds for tissue repair models in 2026, that gap between animal evidence and human data is the central challenge. This article examines the best research peptides for tissue repair: comparing BPC‑157, TB‑500, GHK‑Cu, and Glow/Klow blends for in‑vitro and animal models, covering mechanisms, model selection, reconstitution ranges, and purity considerations.

Key Takeaways

  • BPC‑157, TB‑500, and GHK‑Cu each target a distinct phase of tissue repair, making them complementary rather than redundant.
  • GLOW blends combine all three peptides; KLOW adds the anti-inflammatory tripeptide KPV for a broader repair profile.
  • Preclinical evidence is robust, but human clinical data remains extremely limited — these compounds are for research use only.
  • Purity verification and proper reconstitution are non-negotiable for reproducible in-vitro and animal model results.
  • None of these peptides are FDA-approved for medical use in tissue repair contexts as of 2026.

Key Takeaways


Mechanisms of Action: What Each Peptide Does

Understanding why these peptides are considered among the best research peptides for tissue repair starts with their distinct biological pathways.

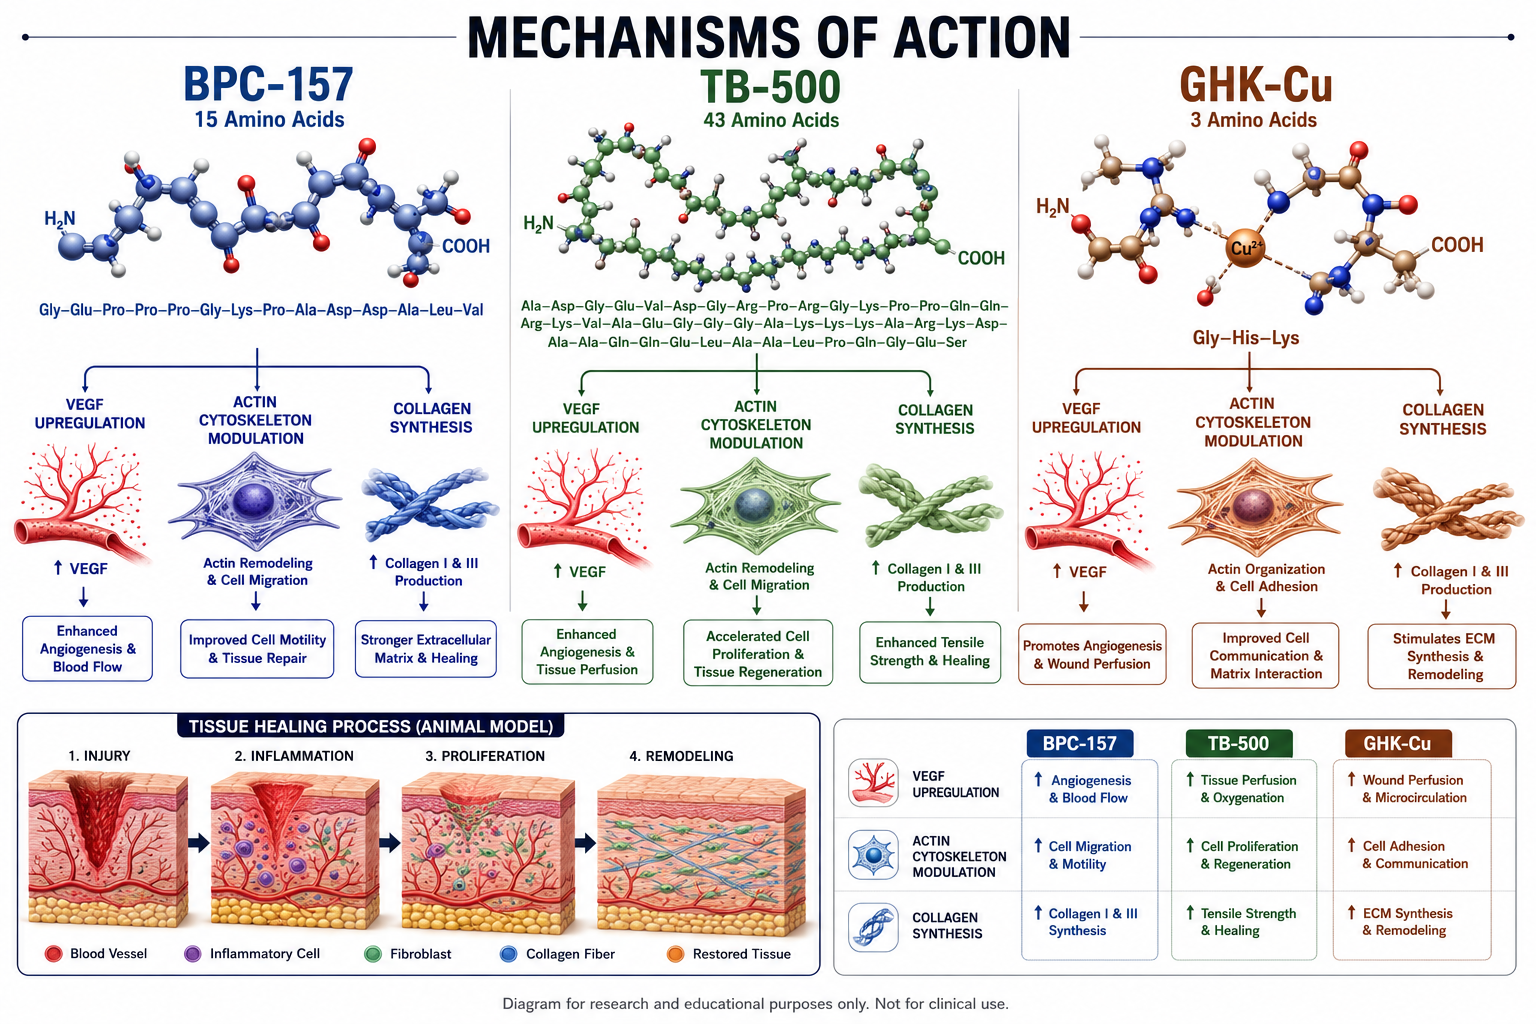
BPC‑157 (Body Protection Compound 157) is a 15-amino-acid synthetic peptide derived from a gastric protein. Its primary mechanism involves upregulating vascular endothelial growth factor (VEGF), which drives angiogenesis — the formation of new blood vessels. In animal models, this translates to accelerated healing across tendons, muscles, ligaments, bones, and gut mucosa. Researchers can explore the BPC-157 research overview for detailed preclinical data summaries.

TB‑500 (Thymosin Beta‑4 fragment) works differently. It modulates the actin cytoskeleton, facilitating cell migration and differentiation. This makes it particularly relevant in wound-closure and muscle-repair models where cellular mobility is rate-limiting.

GHK‑Cu (Glycine-Histidine-Lysine copper complex) focuses on the reconstruction phase. It stimulates collagen synthesis and extracellular matrix remodeling. Researchers studying dermal and connective tissue models will find the GHK-Cu extracellular matrix research a useful reference. The copper chelation component also appears to modulate gene expression related to tissue remodeling.

Peptide Primary Mechanism Key Repair Phase
BPC‑157 VEGF upregulation, angiogenesis Vascularization
TB‑500 Actin modulation, cell migration Proliferation
GHK‑Cu Collagen synthesis, ECM remodeling Reconstruction

Comparing GLOW and KLOW Blends for Research Models

Comparing GLOW and KLOW Blends for Research Models

The GLOW blend combines BPC‑157, TB‑500, and GHK‑Cu in a single formulation, targeting all three stages of the repair cascade sequentially. This multi-phase approach is the core rationale behind proprietary blends — rather than isolating one mechanism, researchers can observe how overlapping pathways interact. The GLOW and KLOW peptide blend overview provides composition details relevant to experimental design.

The KLOW blend extends GLOW by adding KPV, a tripeptide (Lysine-Proline-Valine) with documented anti-inflammatory properties. In models where inflammation is a confounding variable — such as inflammatory bowel or skin wound models — KLOW may offer a more controlled environment for observing net repair outcomes.

Important note: No published clinical trials have evaluated GLOW or KLOW blends in human subjects. Both are marketed strictly for in-vitro research purposes and are not intended for human or veterinary use.

For researchers interested in longevity-adjacent tissue repair themes, the GLOW blend longevity research themes page outlines how these compounds intersect with broader aging biology questions.


Model Selection, Reconstitution, and Purity Considerations

Model Selection, Reconstitution, and Purity Considerations

Selecting the right model is as critical as selecting the peptide. For in-vitro work, cell migration assays (scratch assays), tube formation assays for angiogenesis, and collagen gel contraction models are the most common formats aligned with BPC‑157, TB‑500, and GHK‑Cu mechanisms respectively.

For animal models, rodent tendon transection, excisional wound, and colitis models dominate the published literature on BPC‑157. TB‑500 has shown relevance in cardiac and skeletal muscle injury models. GHK‑Cu is frequently evaluated in dermal punch-biopsy models.

Reconstitution guidance (for research use only):

  • Peptides should be reconstituted with bacteriostatic water or sterile saline.
  • Typical working concentrations in cell culture range from 1 nM to 1 µM depending on the assay.
  • Avoid repeated freeze-thaw cycles; aliquot prior to storage at -20°C.

Purity is the most overlooked variable in peptide research reproducibility. Researchers should require certificates of analysis (CoA) confirming HPLC purity of at least 98% and mass spectrometry confirmation. The quality testing protocols page outlines what rigorous third-party verification looks like in practice. For broader peptide sourcing context, peptide blend research options can help orient purchasing decisions.

Researchers exploring adjacent repair-related compounds may also find the TB-500 and BPC-157 regeneration research page useful for comparative study design.


Conclusion

The best research peptides for tissue repair — BPC‑157, TB‑500, GHK‑Cu, and Glow/Klow blends for in‑vitro and animal models — each bring distinct, well-characterized mechanisms to the repair cascade. BPC‑157 drives vascularization, TB‑500 enables cell migration, and GHK‑Cu rebuilds the extracellular matrix. GLOW and KLOW blends combine these actions, with KLOW adding anti-inflammatory KPV for more complex inflammatory models.

Actionable next steps for researchers:

  • Match peptide selection to the specific repair phase your model targets.
  • Demand third-party CoA documentation with HPLC and mass spec data before ordering.
  • Design controls that isolate individual peptide contributions when using blends.
  • Remain current on regulatory status — none of these compounds are approved for human use as of 2026.

Rigorous experimental design, verified purity, and clear model alignment remain the foundation of reproducible tissue repair research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Best-Research-Peptides-for-Tissue-Repair-Comparing-BPC‑157-TB‑500-GHK‑Cu-and-GlowKlow-Blends-for-In‑Vitro-and-Animal-Models.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-08 13:04:002026-07-20 15:03:37Best Research Peptides for Tissue Repair: Comparing BPC‑157, TB‑500, GHK‑Cu, and Glow/Klow Blends for In‑Vitro and Animal Models
GHK-Cu Peptide Mechanism: Copper Binding, Extracellular Matrix Signaling, and Tissue-Repair Research

GHK-Cu Peptide Mechanism: Copper Binding, Extracellular Matrix Signaling, and Tissue-Repair Research

June 8, 2026/0 Comments/by Pure Tested

Plasma levels of GHK — the tripeptide glycyl-L-histidyl-L-lysine — drop by roughly 60% between the ages of 20 and 60. That single biochemical fact helps explain why researchers studying regenerative biology keep returning to the GHK-Cu peptide mechanism: copper binding, extracellular matrix signaling, and tissue-repair research as a framework for understanding age-related decline in wound closure, collagen turnover, and cellular defense.

Scientific diagram-style landscape image () illustrating GHK-Cu copper binding chemistry: a three-dimensional molecular

Key Takeaways

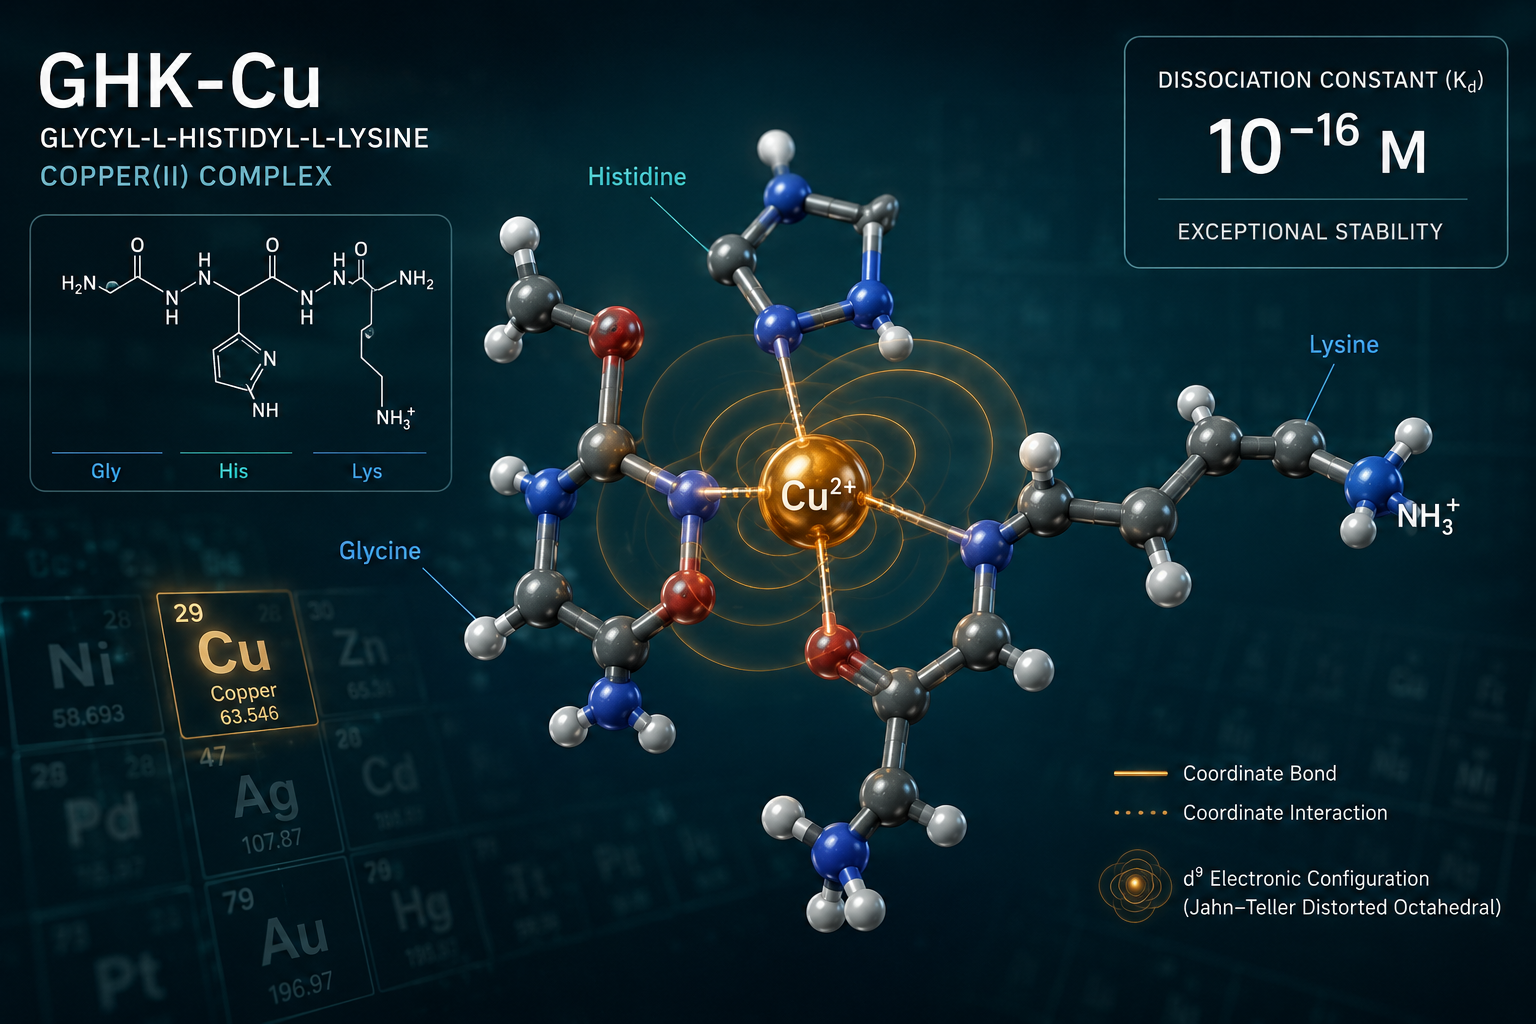
  • GHK-Cu binds copper(II) with extraordinary affinity (dissociation constant near 10⁻¹⁶ M), enabling targeted copper delivery to tissues.
  • The peptide modulates expression of more than 4,000 human genes, influencing repair, inflammation, and antioxidant pathways simultaneously.
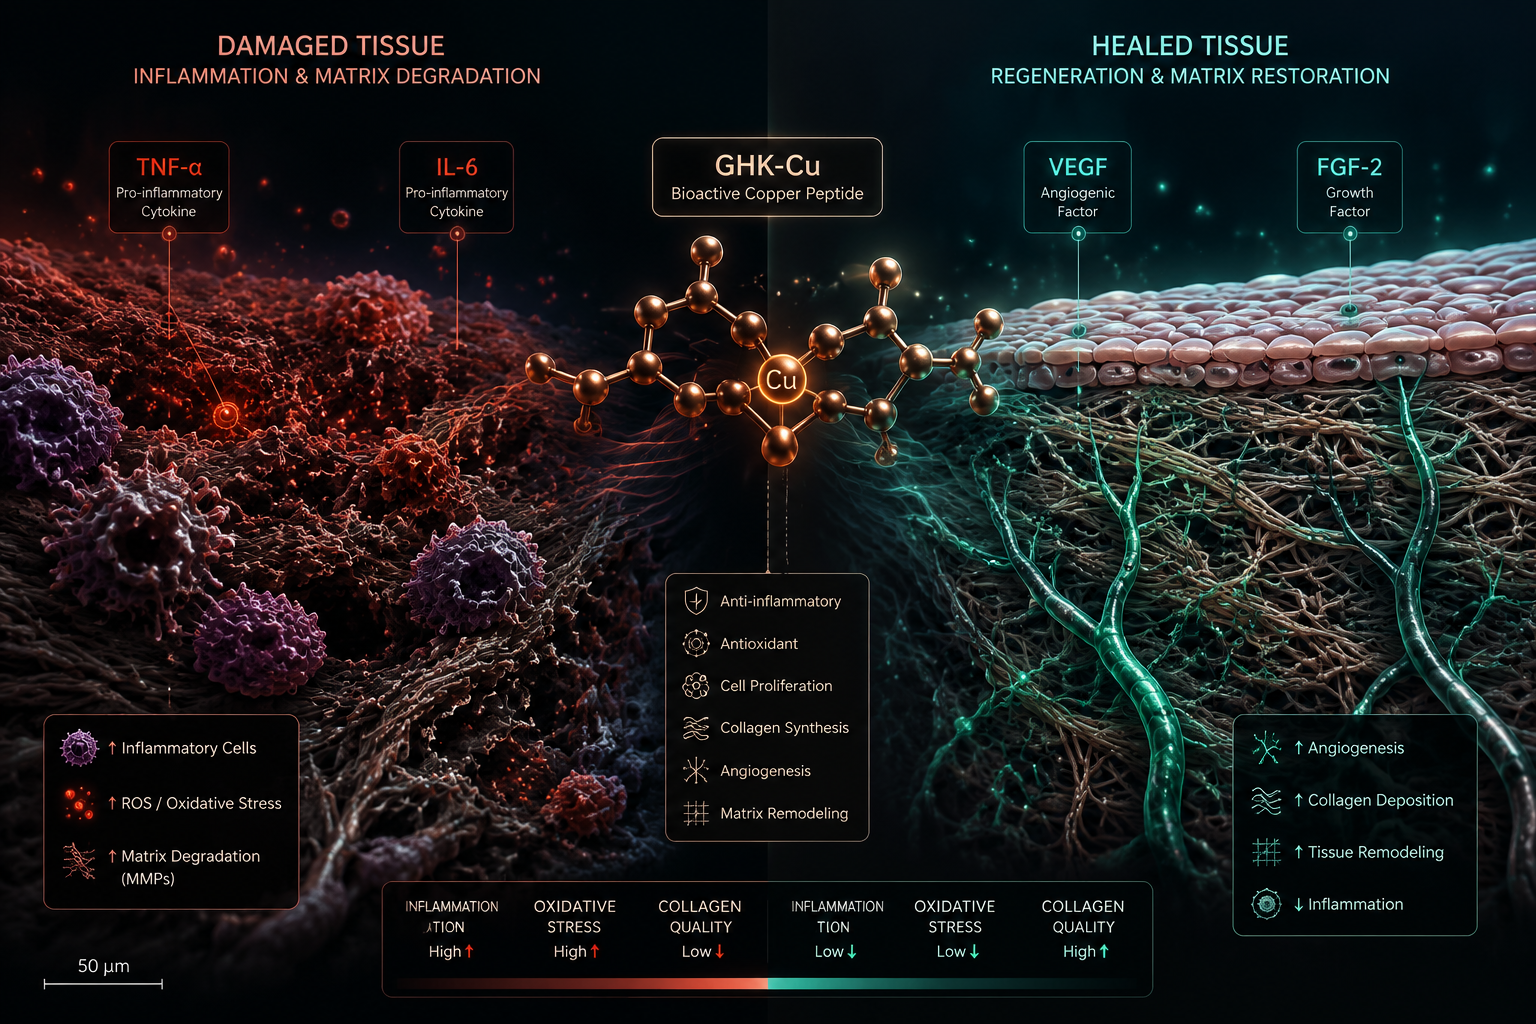
  • GHK-Cu activates TGF-beta signaling and upregulates VEGF and FGF-2, driving collagen synthesis and angiogenesis.
  • Anti-inflammatory effects stem from NF-kB pathway inhibition, reducing TNF-alpha and IL-6 production.
  • Unlike receptor-targeted peptides, GHK-Cu acts primarily through direct extracellular matrix interaction and redox chemistry.

How the GHK-Cu Copper Binding Mechanism Works

The tripeptide GHK (Gly-His-Lys) naturally forms a stable complex with copper(II) ions. What makes this binding unusual is its strength: the dissociation constant sits near 10⁻¹⁶ M, placing it among the tightest metal-peptide interactions documented in biochemistry. This affinity is not incidental — it is the structural basis for everything else the molecule does.

The histidine residue provides the primary coordination site for Cu²⁺, while the glycine and lysine flanking residues stabilize the complex geometrically. The result is a molecule that can transport bioavailable copper to target tissues without releasing it prematurely into circulation, where free copper would generate oxidative damage.

Why copper matters here: Copper is an essential cofactor for lysyl oxidase, the enzyme that crosslinks collagen and elastin fibers in connective tissue. Without adequate copper delivery, newly synthesized matrix proteins remain structurally weak. GHK-Cu effectively solves a delivery problem that free copper supplementation cannot address safely.

For researchers comparing copper-dependent mechanisms across peptide classes, the GHK-Cu longevity research themes page provides additional context on how these pathways intersect with aging biology.


Extracellular Matrix Signaling: The Core of GHK-Cu Peptide Mechanism Research

Extracellular Matrix Signaling: The Core of GHK-Cu Peptide Mechanism Research

Most regenerative peptides work by binding a specific receptor. GHK-Cu operates differently. Its primary influence on tissue biology runs through direct extracellular matrix (ECM) interaction combined with downstream gene expression changes — a mechanistic distinction that gives it an unusually broad biological footprint.

Collagen, Elastin, and Decorin Upregulation

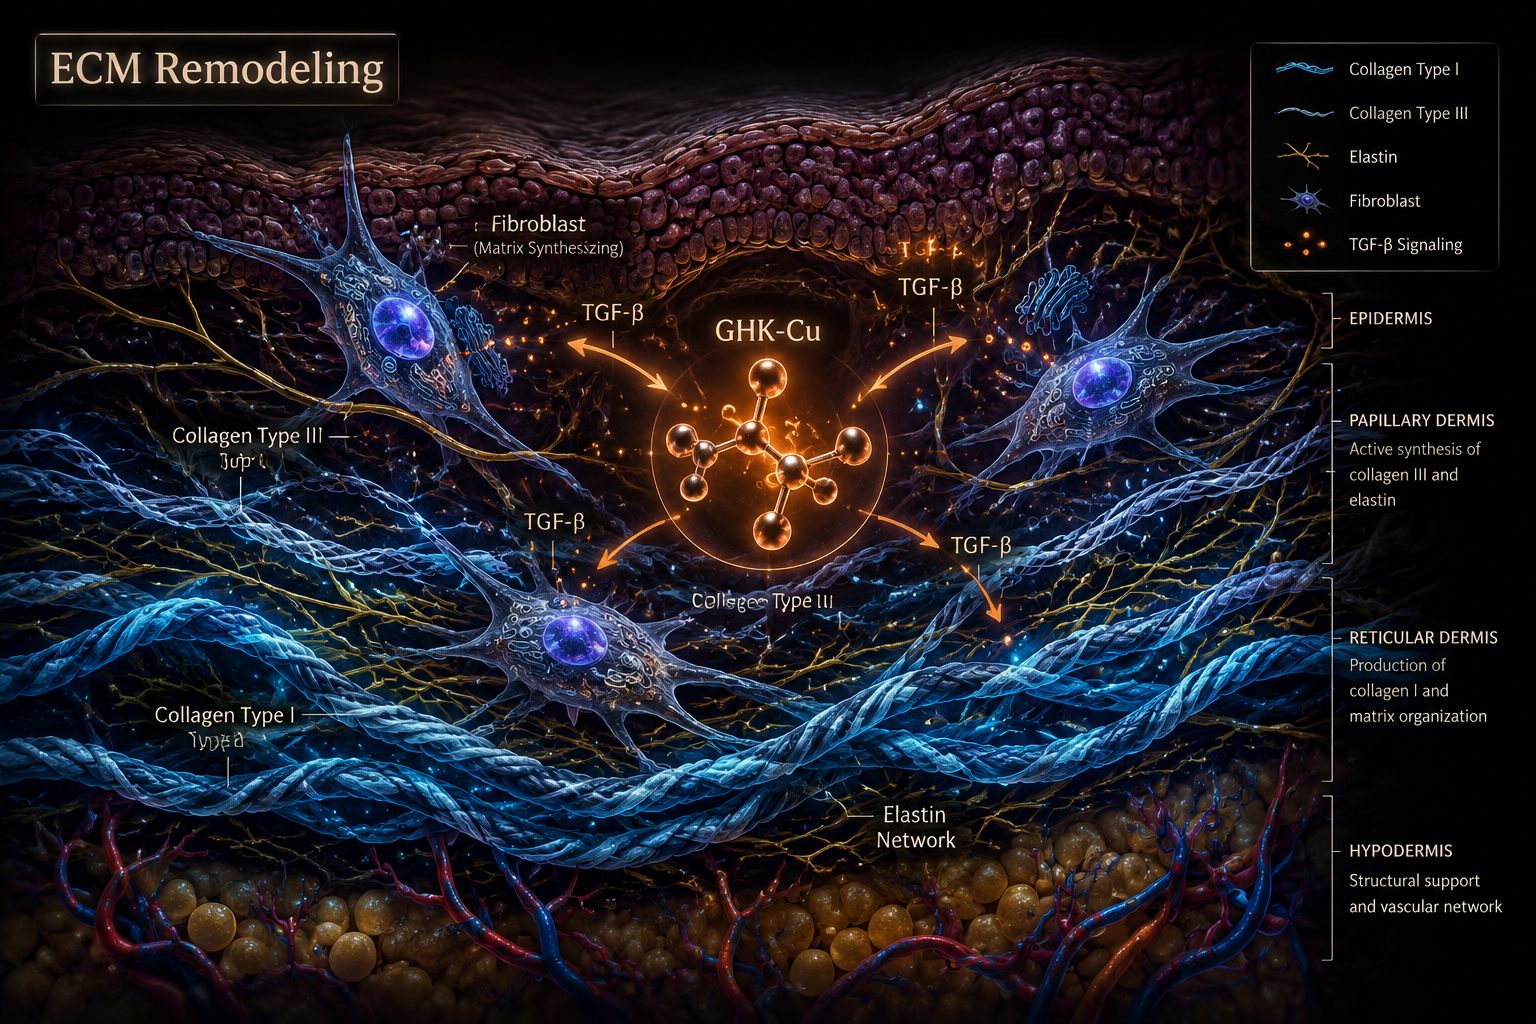
GHK-Cu stimulates synthesis of:

ECM Component Function
Type I Collagen Structural tensile strength in skin and tendons
Type III Collagen Early wound scaffolding, vascular walls
Elastin Tissue recoil and flexibility
Decorin Collagen fiber organization, TGF-beta regulation

This multi-target ECM effect is driven partly through TGF-beta pathway activation. When GHK-Cu engages fibroblasts, it upregulates TGF-beta signaling, which in turn amplifies collagen gene transcription and matrix metalloproteinase (MMP) regulation — clearing damaged matrix while simultaneously building replacement structure.

Gene Expression at Scale

One of the most striking findings in GHK-Cu research is the breadth of its genomic influence. Studies suggest the peptide modulates expression of over 4,000 human genes — approximately 32% of the genome. These include genes governing:

  • Tissue repair and regeneration
  • Antioxidant enzyme production
  • Inflammatory cytokine regulation
  • Neuronal and vascular remodeling

This scale of influence is unusual for a tripeptide and has led researchers to describe GHK-Cu as a biological reset signal rather than a simple growth factor mimic.

Researchers interested in how other peptides influence gene-level repair pathways may find the BPC-157 core peptides documentation and research guide a useful parallel reference.


Tissue-Repair Research: Wound Healing, Inflammation, and Antioxidant Defense

Tissue-Repair Research: Wound Healing, Inflammation, and Antioxidant Defense

The practical research interest in GHK-Cu centers on three interconnected repair processes: accelerating wound closure, suppressing damaging inflammation, and neutralizing oxidative stress.

Angiogenesis and Growth Factor Upregulation

Wound healing requires new blood vessel formation. GHK-Cu upregulates both vascular endothelial growth factor (VEGF) and fibroblast growth factor-2 (FGF-2), two primary drivers of angiogenesis. This vascular recruitment accelerates oxygen and nutrient delivery to healing tissue, shortening repair timelines in preclinical models.

NF-kB Inhibition and Cytokine Control

Chronic inflammation is a major obstacle to tissue repair. GHK-Cu inhibits the NF-kB pathway, which controls transcription of pro-inflammatory cytokines including TNF-alpha and IL-6. By dampening this inflammatory cascade without eliminating it entirely, the peptide creates a biochemical environment that supports repair rather than prolonged destruction.

This mechanism is conceptually related to how other anti-inflammatory peptides operate. For context on related signaling work, see the synergy of LL-37 and MOTS-c research overview.

Superoxide Dismutase and Redox Protection

The copper ion within GHK-Cu serves as a cofactor for superoxide dismutase (SOD), the enzyme responsible for converting damaging superoxide radicals into less harmful molecules. During active tissue repair, oxidative stress is elevated. GHK-Cu's antioxidant contribution through SOD activity helps protect newly forming tissue from free radical damage — a function that complements its matrix-building role.

Researchers studying mitochondrial redox biology alongside copper-peptide mechanisms may also want to review SS-31 mitochondrial research themes for comparative antioxidant pathway data.

"GHK-Cu does not fit neatly into a single pharmacological category — it is simultaneously a copper carrier, a gene modulator, an ECM stimulant, and an antioxidant cofactor."

Age-Related Decline and Research Implications

The drop in endogenous GHK from roughly 200 ng/mL at age 20 to approximately 80 ng/mL by age 60 is not merely a biomarker curiosity. It maps directly onto the well-documented decline in wound healing speed, skin thickness, and regenerative capacity seen in older populations. This correlation has made GHK-Cu a focus of longevity-oriented peptide research in 2026.

Topical formulations have shown measurable improvements in skin elasticity and collagen density in cosmetic studies. Controlled human trials for systemic or injectable applications remain limited, which represents an active gap in the research landscape. Those looking to explore available research-grade material can review GHK-Cu peptides for sale and the associated GHK-Cu research documentation.

For broader context on how copper-peptide signaling fits within the wider peptide research landscape, the comprehensive peptide catalog overview offers a useful starting point.


Conclusion

The GHK-Cu peptide mechanism — spanning copper binding, extracellular matrix signaling, and tissue-repair research — represents one of the more mechanistically rich areas in current peptide biology. Its value lies not in a single action but in a coordinated set of effects: precise copper delivery, broad gene expression modulation, TGF-beta and growth factor activation, NF-kB suppression, and SOD-mediated antioxidant defense.

Actionable next steps for researchers:

  • Review preclinical wound-healing and gene expression data before designing any in-vitro protocol.
  • Compare GHK-Cu's ECM-direct mechanism against receptor-mediated peptides like BPC-157 to identify complementary research angles.
  • Monitor the controlled human trial literature, which remains sparse and represents the most significant knowledge gap in 2026.
  • Source only purity-verified, lab-tested material to ensure research data integrity.

Understanding the mechanism at this level of detail is what separates productive research from superficial application — and GHK-Cu rewards that depth of inquiry.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GHK-Cu-Peptide-Mechanism-Copper-Binding-Extracellular-Matrix-Signaling-and-Tissue-Repair-Research.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-08 13:03:252026-07-20 15:03:38GHK-Cu Peptide Mechanism: Copper Binding, Extracellular Matrix Signaling, and Tissue-Repair Research
What Is GLP2-T Peptide? Research Use, Gut Barrier Biology, and Experimental Applications

What Is GLP2-T Peptide? Research Use, Gut Barrier Biology, and Experimental Applications

June 8, 2026/0 Comments/by Pure Tested

Gut barrier failure is now linked to dozens of systemic conditions, from inflammatory bowel disease to metabolic dysfunction — and researchers are increasingly focused on peptide-based tools that can probe and potentially restore intestinal integrity. Among those tools, GLP2-T peptide has earned serious attention. Understanding what is GLP2-T peptide, its research use, gut barrier biology, and experimental applications is essential for any researcher working at the intersection of incretin biology and mucosal physiology in 2026.

Key Takeaways

  • GLP2-T is a research-grade analog of glucagon-like peptide-2 (GLP-2), a 33-amino acid hormone secreted by intestinal L-cells
  • Its primary research interest centers on gut mucosal growth, tight junction regulation, and intestinal barrier integrity
  • GLP-2 receptor signaling operates through indirect pathways involving IGF-1, IGF-2, and ErbB ligands
  • Experimental models include Caco-2 cell cultures, aged animal models, and chemotherapy-induced mucositis studies
  • GLP2-T is intended strictly for laboratory research and is not approved for human therapeutic use

GLP-2 Biology: The Foundation Behind GLP2-T

GLP-2 is a 33-amino acid peptide produced and released by enteroendocrine L-cells located in the distal small intestine and colon. Nutrient intake — particularly fat and carbohydrates — triggers its secretion. Once released, GLP-2 acts primarily on the gastrointestinal tract, where it drives two major effects: stimulation of intestinal crypt cell proliferation and inhibition of epithelial apoptosis. The combined result is a measurable increase in mucosal surface area.

GLP2-T refers to a stabilized or modified analog of native GLP-2 designed for research use. The "T" designation typically signals a structural modification that extends the peptide's half-life or improves receptor binding stability, making it more practical for controlled experimental settings.

For researchers already familiar with incretin biology, the GLP-1 peptide research landscape provides useful context — GLP-1 and GLP-2 are co-secreted from the same L-cells but act on entirely different receptor systems and tissue targets.

GLP-2 Biology: The Foundation Behind GLP2-T


Gut Barrier Biology: How GLP2-T Research Targets Tight Junctions

The gut epithelial barrier is not simply a physical wall. It is a dynamic, protein-regulated interface that controls what passes from the intestinal lumen into systemic circulation. Tight junction proteins — particularly claudin-3 and occludin — are the molecular gatekeepers of this barrier.

Research demonstrates that GLP-2 modulates the expression and organization of these tight junction proteins, reducing intestinal permeability. In vitro studies using Caco-2 cell models have shown that GLP-2 enhances barrier formation and protects against TNF-alpha-induced disruptions, a key finding for inflammatory disease research.

The receptor mechanism adds an important layer of complexity. The GLP-2 receptor (GLP-2R) is not expressed directly on proliferating crypt cells. Instead, GLP-2 acts through indirect pathways, signaling via:

Mediator Role in GLP-2 Signaling
IGF-1 and IGF-2 Drive crypt cell proliferation downstream
ErbB ligands Support epithelial repair and growth signaling
Enteric neurons Relay signals to mucosal tissue
Subepithelial myofibroblasts Coordinate structural barrier responses

This indirect signaling architecture makes GLP2-T particularly interesting for researchers studying paracrine gut biology. It also connects naturally to broader peptide research themes in gut and tissue repair.


Experimental Applications of GLP2-T in Research Models

Experimental Applications of GLP2-T in Research Models

Understanding what is GLP2-T peptide's research use, gut barrier biology, and experimental applications requires looking at the model systems where it has shown the most consistent activity.

Aged Animal Models
Studies in aged rats show that GLP-2 administration improves intestinal mucosal barrier function, suggesting potential relevance for age-related intestinal decline. This positions GLP2-T alongside other longevity-oriented research compounds.

Chemotherapy-Induced Mucositis
GLP-2 has been associated with reduced severity of chemotherapy-induced mucositis in experimental settings, pointing to a supportive role in oncology-adjacent research.

Inflammatory Bowel Disease Models
GLP-2 reduces mucosal permeability, enhances nutrient absorption, and promotes intestinal healing in models of short bowel syndrome and IBD. Researchers exploring GLP-3 and incretin research themes will find GLP2-T a logical parallel compound to study.

Blood Flow Regulation
GLP-2 also modulates intestinal blood flow, adding a vascular dimension to its gut-protective profile.

For researchers exploring dual receptor agonism in the GLP family, GLP2-T offers a clean, single-receptor reference point that clarifies which effects are GLP-2R-specific.

Experimental Applications of GLP2-T in Research Models

Those sourcing research-grade materials should review options from a verified peptide manufacturer to ensure purity standards appropriate for barrier biology assays.


Conclusion

GLP2-T peptide is a research-grade tool with a well-defined biological target: the intestinal epithelial barrier. Its ability to modulate tight junction proteins, drive mucosal growth through indirect receptor pathways, and protect against inflammatory insults makes it a high-value compound for gut biology research in 2026.

Actionable next steps for researchers:

  • Review Caco-2 permeability assay protocols before designing GLP2-T barrier studies
  • Compare GLP2-T activity against GLP-1 analogs to isolate receptor-specific effects
  • Explore aged-model or mucositis study designs where GLP-2 effects are most documented
  • Source only from suppliers with verified purity documentation; browse all available peptides for research use to build a complete experimental panel
  • Stay current with new developments in peptide research as GLP-2 analog science continues to evolve

GLP2-T is not a therapeutic product — it is a precision research instrument. Used correctly within controlled laboratory settings, it opens a clear window into some of the most clinically relevant questions in gastrointestinal biology today.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/What-Is-GLP2-T-Peptide-Research-Use-Gut-Barrier-Biology-and-Experimental-Applications.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-08 13:03:242026-07-20 15:03:38What Is GLP2-T Peptide? Research Use, Gut Barrier Biology, and Experimental Applications
Carbohydrate Antigens, GLP Peptides, and Gut Hormone Biology: How GLP‑2‑T and GLP‑3 Retatrutide Are Used in Laboratory Metabolic Models

Carbohydrate Antigens, GLP Peptides, and Gut Hormone Biology: How GLP‑2‑T and GLP‑3 Retatrutide Are Used in Laboratory Metabolic Models

June 8, 2026/0 Comments/by Pure Tested

Researchers searching for carbohydrate antigens often arrive at a broader and more complex story than they expected — one that connects gut-surface glycoproteins, enteroendocrine signaling, and next-generation incretin peptides into a single field of immunometabolic inquiry. Understanding Carbohydrate Antigens, GLP Peptides, and Gut Hormone Biology: How GLP‑2‑T and GLP‑3 Retatrutide Are Used in Laboratory Metabolic Models requires tracing how the intestinal epithelium functions simultaneously as an immune interface and a hormone-secreting organ.

Key Takeaways

  • Carbohydrate antigens on gut epithelial surfaces are structurally linked to the same L cells that secrete GLP-1 and GLP-2 peptides
  • GLP-2 (sometimes labeled GLP-2-T in research contexts) is a short-lived postprandial hormone with a half-life of roughly seven minutes, primarily driving intestinal growth
  • Retatrutide, informally called GLP-3 in research communities, is a triple agonist targeting GLP-1, GIP, and glucagon receptors simultaneously
  • The gut microbiome modulates incretin secretion through short-chain fatty acid (SCFA) production, linking microbial ecology to metabolic peptide biology
  • Laboratory metabolic models use these peptides to study obesity, glucose homeostasis, liver fat, and intestinal barrier function

Key Takeaways

The Gut Epithelium as Both Antigen Display and Hormone Factory

The intestinal lining does two jobs at once. Its surface is decorated with carbohydrate antigens — complex sugar chains attached to glycoproteins and glycolipids — that interact with immune cells, pathogens, and the gut microbiome. At the same time, specialized enteroendocrine L cells embedded in that same epithelium sense luminal nutrients and release proglucagon-derived peptides (PGDPs), including GLP-1 and GLP-2.

This dual role is not coincidental. The same nutrient-sensing machinery that triggers incretin release also modulates surface antigen expression. Short-chain fatty acids produced by gut bacteria bind to free fatty acid receptors on L cells, stimulating GLP-1 and peptide YY (PYY) secretion. Disruptions in this axis — whether from dysbiosis, inflammation, or altered glycan expression — impair glucose homeostasis at a fundamental level.

GLP-2, released alongside GLP-1 from the same L cells, has a distinct role: it promotes intestinal mucosal growth, enhances barrier integrity, and reduces gut permeability. Its half-life is approximately seven minutes in native form, which is why research models use stabilized analogs (sometimes designated GLP-2-T) to study its effects over longer windows. For researchers exploring generations of GLP-1 analogs and their differences, understanding GLP-2's parallel biology adds important context.

"The intestinal epithelium is not a passive barrier — it is an active endocrine and immunological organ whose carbohydrate surface determines how both pathogens and peptide hormones interact with the host."

GLP‑2‑T and GLP‑3 Retatrutide in Laboratory Metabolic Models

GLP‑2‑T and GLP‑3 Retatrutide in Laboratory Metabolic Models

This is where Carbohydrate Antigens, GLP Peptides, and Gut Hormone Biology: How GLP‑2‑T and GLP‑3 Retatrutide Are Used in Laboratory Metabolic Models becomes directly actionable for research design.

Retatrutide (LY3437943), informally called GLP-3 to emphasize its triple mechanism, is a 39-amino-acid synthetic peptide. It simultaneously activates GLP-1, GIP, and glucagon receptors — a profile that distinguishes it sharply from semaglutide (GLP-1 only) and tirzepatide (GLP-1 plus GIP). Its structure includes 2-aminoisobutyric acid (Aib) substitutions and a C20 fatty-diacid moiety, synthesized via solid-phase peptide synthesis for research-grade precision.

Phase 2 data showed dose-dependent reductions in body weight, liver fat content, and fasting glucose, alongside improvements in body composition. The glucagon receptor component adds a metabolic dimension absent in earlier incretin therapies — driving hepatic glucose output modulation and energy expenditure in ways that pure GLP-1 agonism cannot replicate. Researchers can explore the GLP-3 triple agonist research overview for deeper mechanistic detail.

Comparing Key Metabolic Peptides Used in Research Models

Peptide Receptor Targets Primary Research Focus
GLP-2 / GLP-2-T GLP-2R Intestinal growth, barrier integrity
Tirzepatide GLP-1R + GIPR Glycemic control, weight loss
Retatrutide (GLP-3) GLP-1R + GIPR + GCGR Weight, liver fat, energy expenditure
MOTS-C AMPK via AICAR Mitochondrial metabolism

For researchers also studying mitochondrial metabolic pathways, MOTS-C as a mitochondrial-derived peptide represents a complementary but mechanistically distinct tool. Similarly, the cagrilintide and GLP-1 synergy research illustrates how combination approaches are reshaping metabolic model design in 2026.

Applying This Framework to Advanced Immunometabolic Research

Applying This Framework to Advanced Immunometabolic Research

The convergence of Carbohydrate Antigens, GLP Peptides, and Gut Hormone Biology: How GLP‑2‑T and GLP‑3 Retatrutide Are Used in Laboratory Metabolic Models opens specific experimental opportunities.

First, carbohydrate antigen panels (such as CA 19-9 or Lewis antigen variants) are increasingly used alongside incretin assays to characterize gut epithelial status in metabolic disease models. Altered glycan expression correlates with L-cell density changes, which directly affects GLP-1 and GLP-2 output.

Second, receptor distribution matters. GLP-1R, GLP-2R, and GIPR are expressed in distinct cell populations within the gastrointestinal tract, each with unique downstream signaling circuits. Designing a model that conflates these receptors produces unreliable data. Researchers using lab-tested peptides for metabolic studies should verify receptor specificity before drawing mechanistic conclusions.

Third, the gut microbiome variable cannot be ignored. SCFA-driven incretin secretion means that germ-free versus colonized animal models will produce meaningfully different GLP peptide profiles, even when the same compound is administered.

For researchers sourcing compounds, reviewing peptide supplier comparisons and ensuring purity documentation is essential before beginning any gut hormone biology protocol.

Conclusion

The bridge between carbohydrate antigen biology and GLP peptide research is not theoretical — it is structural. The same intestinal epithelium that displays immunologically active glycan antigens is the tissue that secretes GLP-1, GLP-2, and the hormones that next-generation compounds like Retatrutide are designed to engage. For researchers building metabolic models in 2026, the actionable steps are clear: characterize epithelial antigen status alongside incretin output, distinguish receptor targets precisely when selecting GLP-2-T versus GLP-3 analogs, and account for microbiome-driven SCFA variability in experimental design. Sourcing research-grade peptides with verified purity and cross-referencing mechanistic data from the GLP-1 dual receptor agonism research breakdown will strengthen the validity of any gut hormone biology protocol.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Carbohydrate-Antigens-GLP-Peptides-and-Gut-Hormone-Biology-How-GLP‑2‑T-and-GLP‑3-Retatrutide-Are-Used-in-Laboratory-Metabolic-Models.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-08 13:03:242026-07-20 15:03:47Carbohydrate Antigens, GLP Peptides, and Gut Hormone Biology: How GLP‑2‑T and GLP‑3 Retatrutide Are Used in Laboratory Metabolic Models
Page 63 of 81«‹6162636465›»
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top