Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: hpt axis

Enclomiphene and LH/FSH Pulsatility: A Sampling Design for Separating Endocrine Feedback From Circadian Variation

Enclomiphene and LH/FSH Pulsatility: A Sampling Design for Separating Endocrine Feedback From Circadian Variation

October 16, 2026/0 Comments/in Uncategorized/by

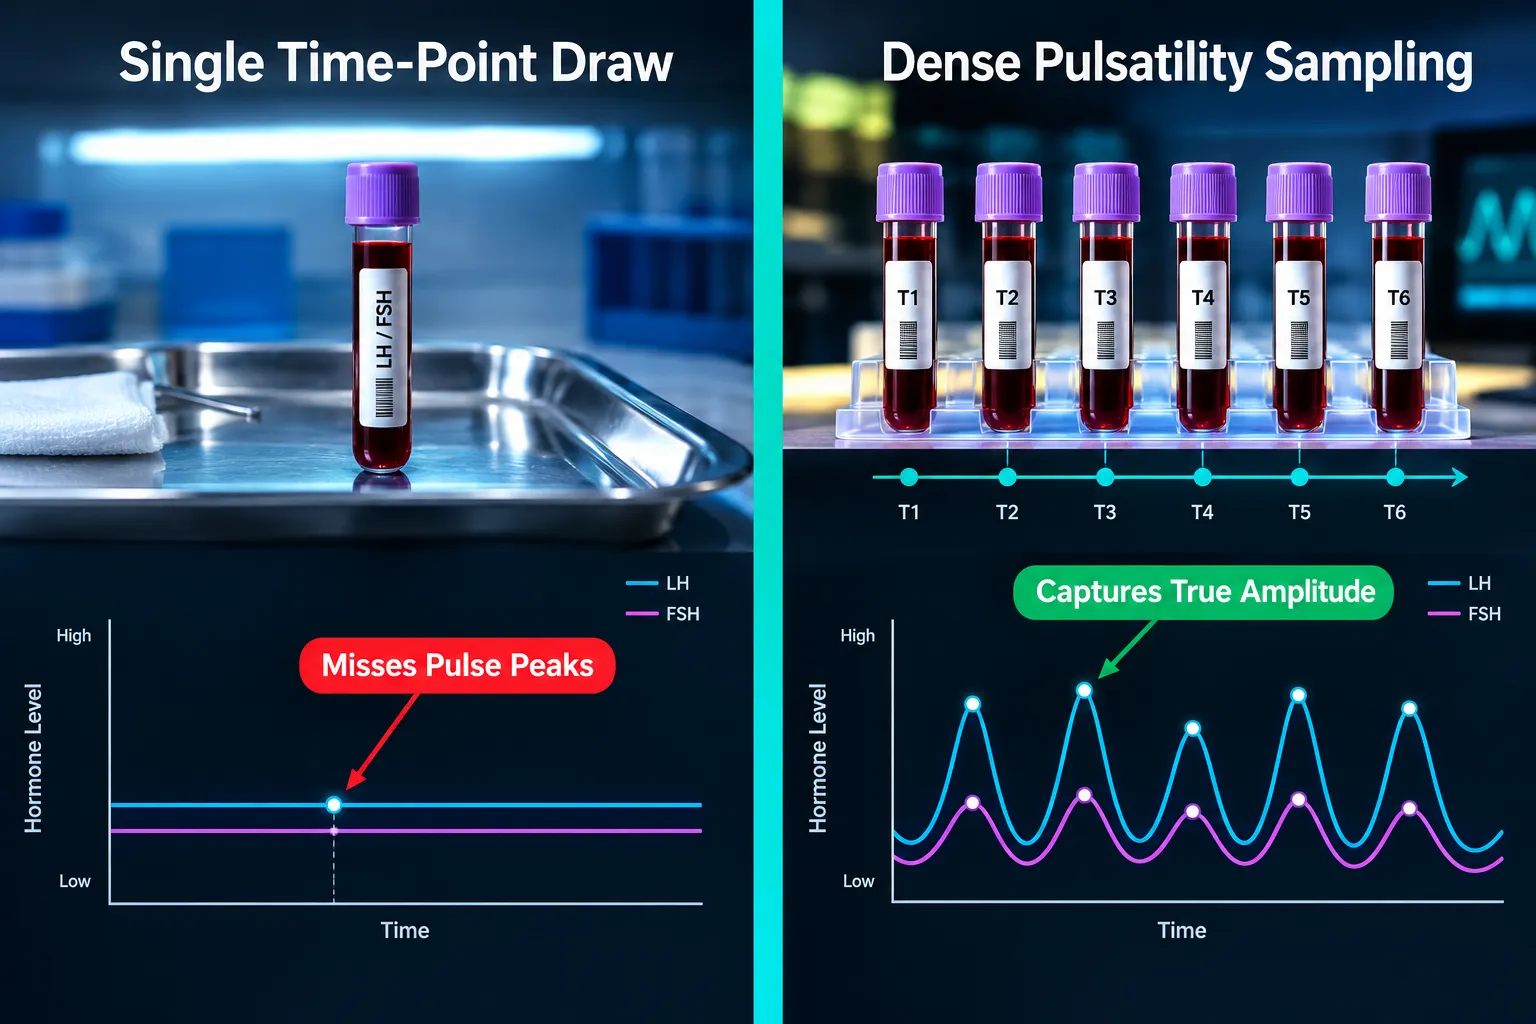
A single morning blood draw tells only a fraction of the story. When a 25 mg dose of enclomiphene pushed LH from 5.3 to 11.9 mIU/mL and FSH from 9.4 to 14.9 mIU/mL in one controlled trial, researchers noted something equally important: serum enclomiphene concentration peaks did not line up with LH secretion peaks. That mismatch is not a flaw in the drug, it is a warning about how endocrine data gets collected and interpreted.

Understanding enclomiphene and LH/FSH pulsatility: a sampling design for separating endocrine feedback from circadian variation requires thinking beyond single-point measurements and toward the temporal architecture of gonadotropin secretion.

Key Takeaways

  • LH and FSH are released in discrete pulses, not steady streams, making single-timepoint draws unreliable.
  • Enclomiphene's effect on gonadotropin levels can outlast its serum concentration peak, complicating sparse sampling.
  • Capturing true pulsatility requires blood draws every 10 minutes over a 4-to-6-hour window.
  • Circadian variation and estradiol-driven negative feedback both shape the LH/FSH signal independently.
  • Dense, multi-day sampling schedules are the only validated way to separate drug effect from biological rhythm.

Why Pulsatile Secretion Makes Hormone Measurement Difficult

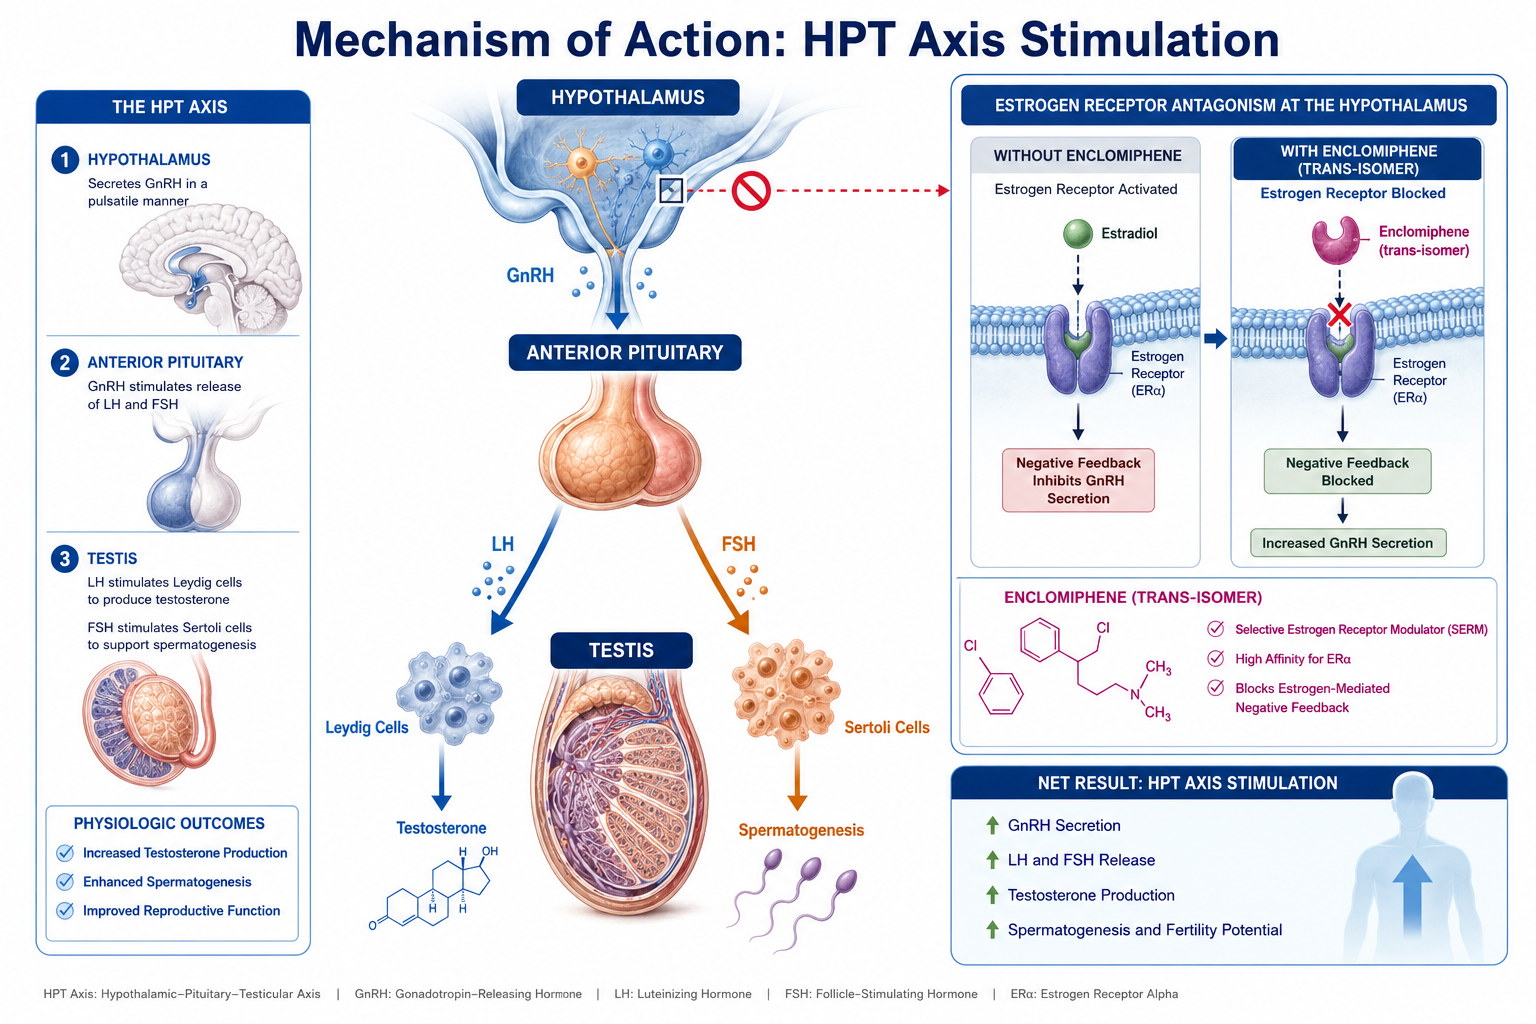
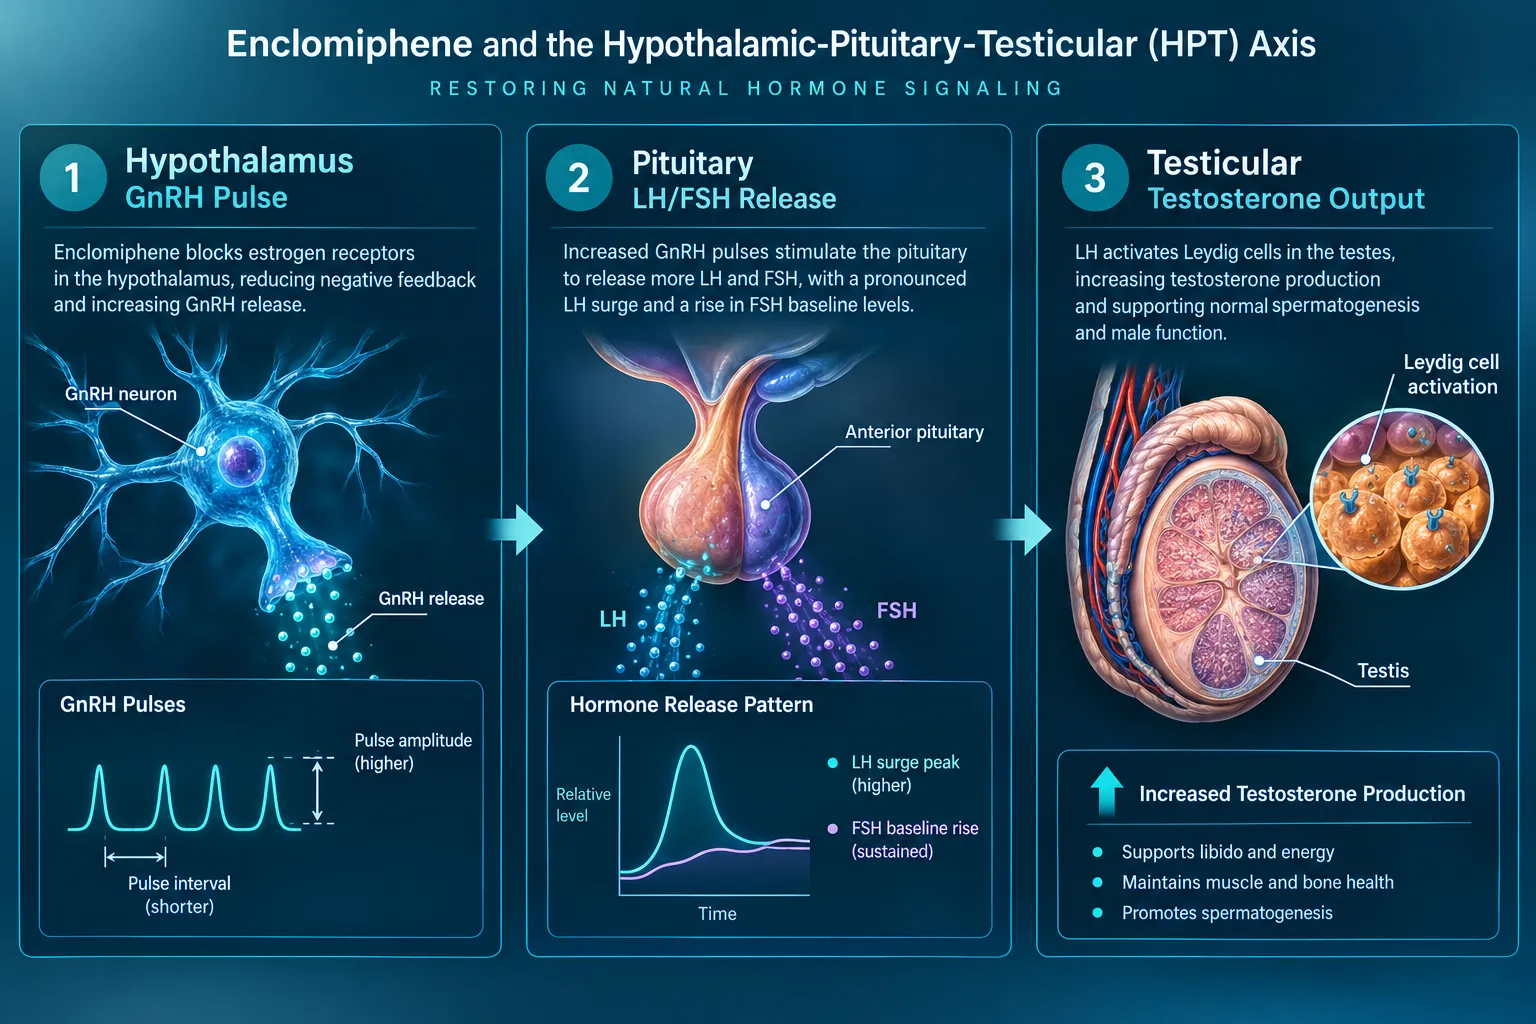
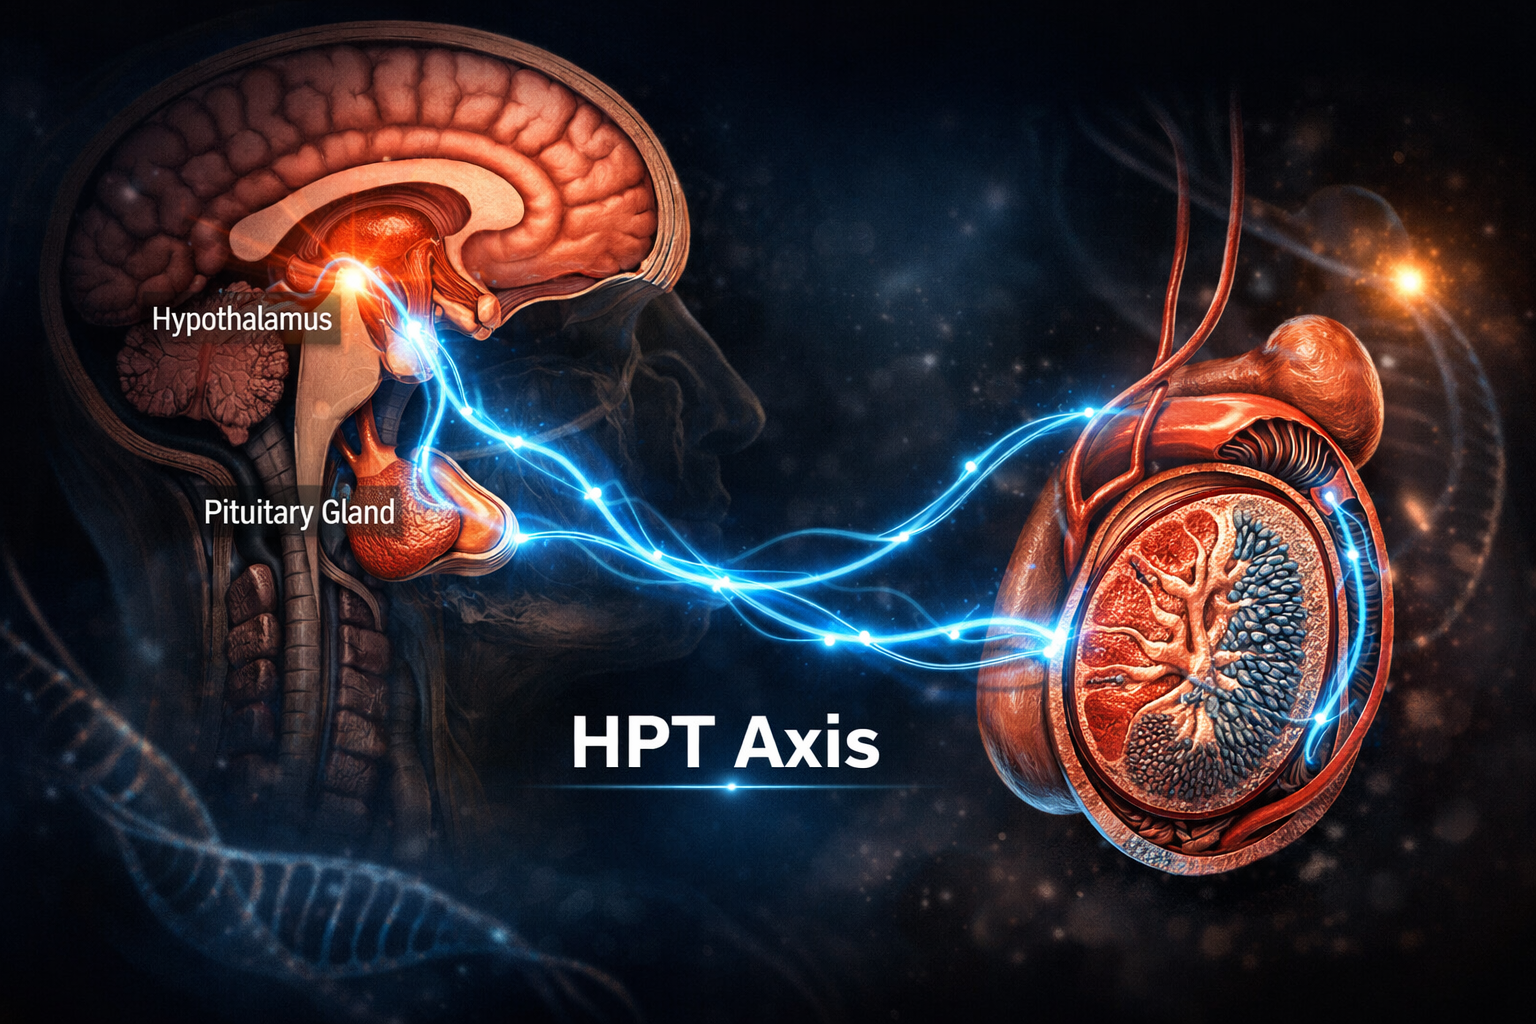
The hypothalamic-pituitary-testicular (HPT) axis does not operate at a flat baseline. GnRH is released from the hypothalamus in discrete bursts, each one triggering a corresponding LH pulse from the pituitary. FSH rises more gradually but still fluctuates. Testosterone, in turn, feeds back to suppress GnRH and LH through two mechanisms: direct androgen feedback and aromatization to estradiol, which exerts its own potent negative feedback at both the hypothalamus and pituitary.

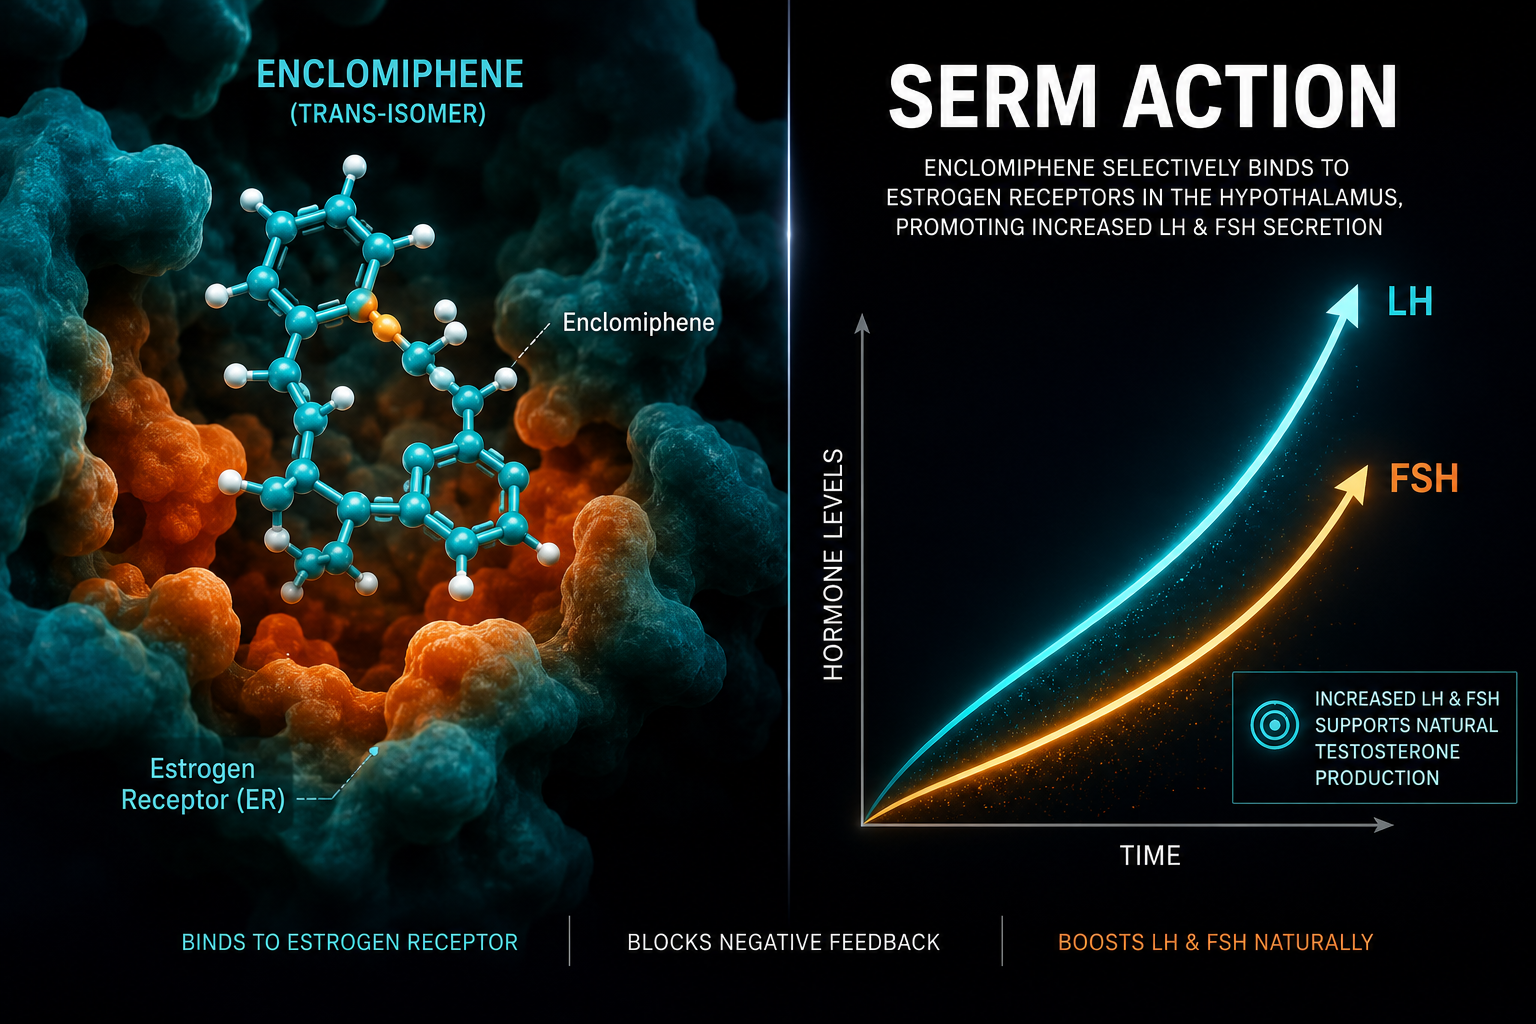
Enclomiphene, the trans-isomer of clomiphene, works by blocking estrogen receptors in the hypothalamus. This reduces the perceived estradiol signal, which the brain interprets as low estrogen, prompting increased GnRH pulsatility and downstream LH and FSH elevation. The result is endogenous testosterone stimulation without suppressing the HPT axis, a key advantage over exogenous testosterone therapy.
Why Pulsatile Secretion Makes Hormone Measurement Difficult

However, this mechanism creates a measurement challenge. The drug acts at the receptor level, not by directly injecting gonadotropins. Its influence on LH pulse amplitude and frequency unfolds over hours and days, not in lockstep with serum drug concentration. An old human study using the en-clomiphene isomer alone found no significant effect on FSH and even a day-8 decrease in LH, a result that highlights how timing, isomer composition, and assay context can dramatically change what gets observed. FDA data further show that LH and FSH remain elevated seven days after dosing begins, meaning the endocrine effect outlasts any single pharmacokinetic peak.

"The drug's receptor-level action means its hormonal footprint can persist long after serum concentration falls, a critical design consideration for any sampling protocol."


The Sampling Design Challenge: Separating Endocrine Feedback From Circadian Variation

The core problem in studying enclomiphene and LH/FSH pulsatility: a sampling design for separating endocrine feedback from circadian variation is that two independent rhythms overlap on the same hormone readout.

Two sources of LH/FSH variation:

Source Timescale Mechanism
GnRH-driven pulses Every 60-120 min Hypothalamic oscillator
Circadian rhythm 24-hour cycle Sleep, cortisol, melatonin
Estradiol feedback Hours to days Aromatization of testosterone
Enclomiphene receptor blockade Days to weeks Estrogen receptor antagonism

A single morning draw captures one point on a curve that oscillates across all four of these timescales simultaneously. To isolate the drug's contribution, the sampling design must account for each layer.

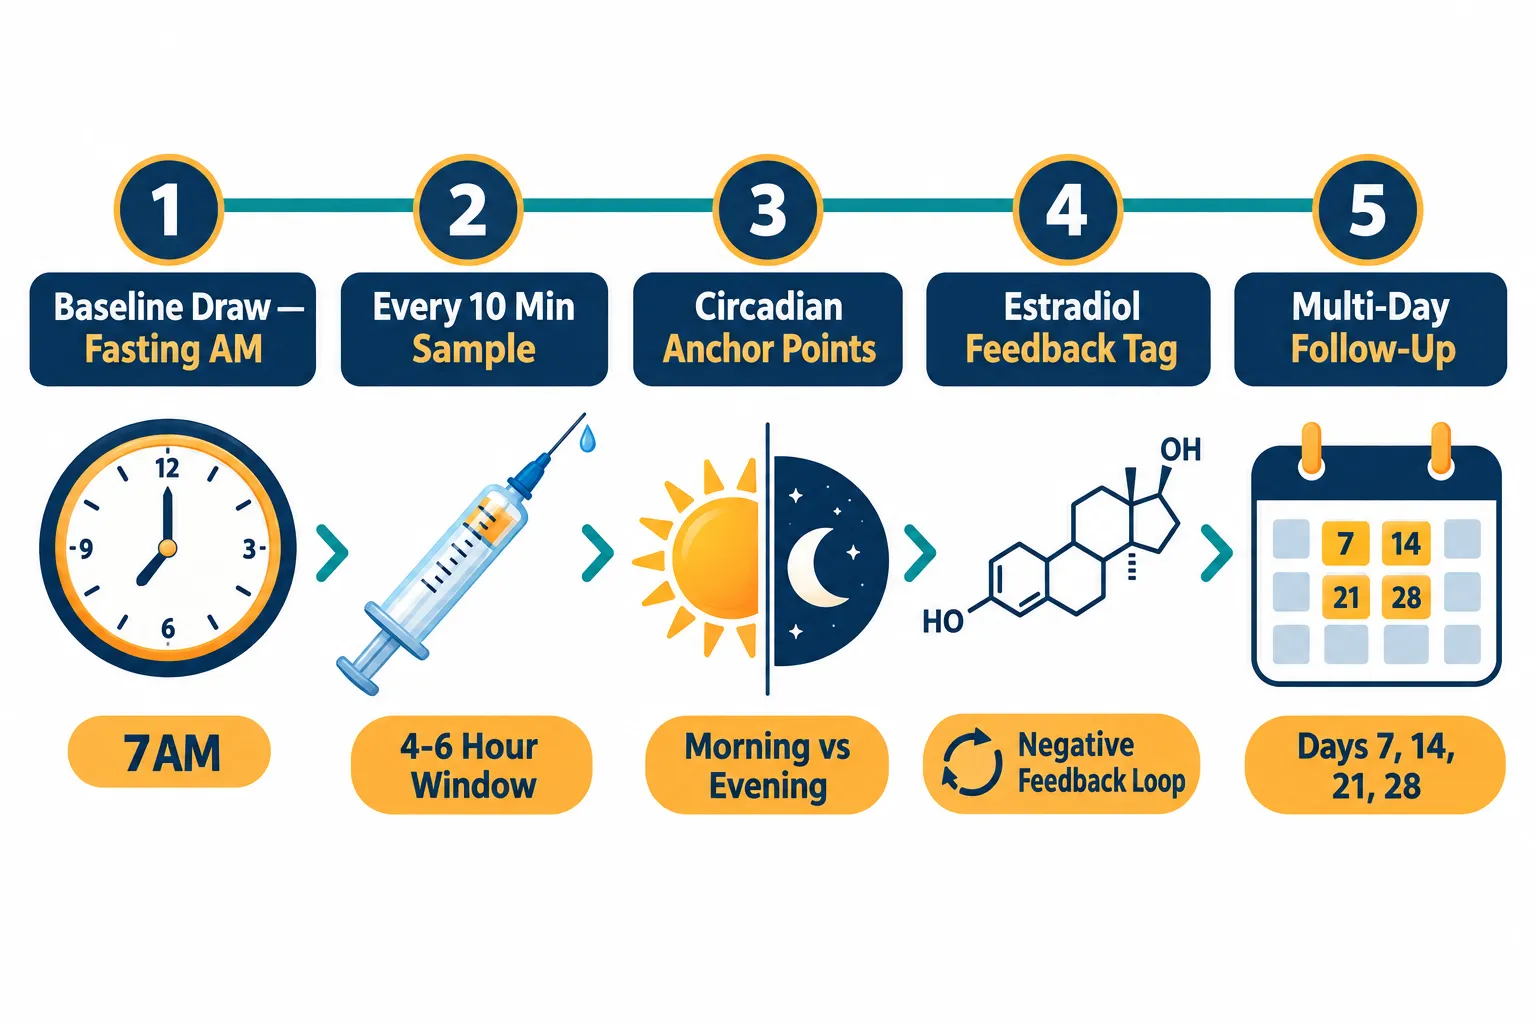
The clearest published guidance on this comes from researchers who specify that blood samples must be collected every 10 minutes for at least 4 to 6 hours to characterize pulsatility properly. This dense-sampling window allows deconvolution algorithms to separate pulse frequency from pulse amplitude, the two parameters most relevant to understanding HPT axis responsiveness under enclomiphene.

A structured longitudinal design used in a JCEM clomiphene study enrolled 12 healthy men aged 25 to 38 and collected samples at baseline plus days 7, 14, 21, 28, 30, 32, 35, 37, 44, 51, and 58. This schedule tracked hormone trajectories during exposure and through washout, providing a practical template for multi-day characterization. Importantly, it also illustrates how combining frequent within-day sampling with multi-day follow-up can distinguish acute pulsatility changes from sustained feedback-loop adaptations.
The Sampling Design Challenge: Separating Endocrine Feedback From Circadian Variation

For researchers and clinicians working with peptide-based hormonal interventions, understanding pulsatile dynamics is relevant beyond enclomiphene alone. Compounds that interact with growth hormone axes, such as those explored in resources comparing Sermorelin vs Tesamorelin or examining Tesamorelin peptide benefits, face analogous sampling challenges because growth hormone is also secreted in pulses with strong circadian anchoring.


Practical Protocol Considerations for 2026 Research and Clinical Monitoring

Translating sampling theory into a workable protocol requires decisions about anchor points, assay selection, and population context.

Recommended protocol elements:

  • Circadian anchor: Fix the sampling window to the same clock time across all subjects (typically 07:00-13:00) to control for diurnal LH variation.
  • Fasting state: Require overnight fasting before each dense-sampling session to reduce metabolic noise.
  • Estradiol co-measurement: Collect estradiol at every timepoint alongside LH and FSH; this allows real-time assessment of negative feedback strength.
  • Baseline characterization: Run at least one dense-sampling session before enclomiphene initiation to establish individual pulse parameters.
  • Multi-day follow-up draws: Add single-timepoint draws on days 7, 14, 21, and 28 to track trajectory between dense sessions.

A 2026 British Society of Sexual Medicine position statement reviewed a cohort of 78 patients and found no statistically significant pre-versus-post differences in testosterone, LH, FSH, or semen parameters, a finding that underscores how much population selection and sampling design influence outcome interpretation. When dense pulsatility data are absent, retrospective cohort analyses like this one cannot distinguish a true null effect from a measurement artifact caused by sparse or poorly timed draws.

The same 2026 position statement supports enclomiphene-class therapy as a fertility-preserving option in men, keeping the clinical stakes of accurate monitoring high. A 2026 review on clomiphene mechanisms reinforces that these agents are used to increase LH, FSH, and testosterone in eugonadal men, a population where baseline pulsatility is already robust and where detecting drug-driven changes requires especially precise sampling.

Practical 2026 clinical guidance continues to recommend morning fasting hormone draws and baseline-plus-follow-up monitoring. These are reasonable heuristics for routine care, but they are not validated pulsatility protocols. The gap between clinical convenience and research-grade measurement is where most interpretive errors occur.

For those interested in how other peptide compounds interact with hormonal feedback loops, resources on CJC-1295 IPA 10mg and the question of whether Ipamorelin and CJC-1295 can be taken together provide useful context on how pulsatile growth hormone secretagogues are timed relative to endogenous rhythms. Similarly, Tesamorelin dosage per day discussions illustrate how dose timing intersects with circadian biology in a directly analogous way.

Mitochondrial peptides such as those discussed in the MOTS-C and Elamipretide resource operate through different axes but reinforce the broader principle that timing and biological rhythm are inseparable from endpoint interpretation.
Practical Protocol Considerations for 2026 Research and Clinical Monitoring


Conclusion

Accurate interpretation of enclomiphene's effects on the HPT axis depends entirely on how and when hormone data are collected. Enclomiphene and LH/FSH pulsatility: a sampling design for separating endocrine feedback from circadian variation is not a theoretical concern, it is a practical barrier to valid conclusions in both clinical trials and individual patient monitoring.

Actionable next steps for researchers and clinicians in 2026:

  1. Replace single-timepoint draws with dense 10-minute sampling sessions of at least 4 to 6 hours when characterizing individual pulsatility responses.
  2. Always co-measure estradiol to quantify the negative feedback contribution independently from the drug effect.
  3. Anchor all sampling sessions to the same circadian time window to eliminate diurnal confounding.
  4. Adopt multi-day follow-up schedules modeled on published longitudinal designs to track trajectory, not just peak response.
  5. Interpret retrospective cohort data cautiously when dense pulsatility sampling was not part of the original design.

The biology of pulsatile gonadotropin secretion is well understood. The gap that remains is methodological, and closing it starts with a better sampling design.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/enclomiphene-and-lh-fsh-pulsatility-a-sampling-design-for-separating-endocrine-f.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-16 13:04:242026-10-16 13:04:24Enclomiphene and LH/FSH Pulsatility: A Sampling Design for Separating Endocrine Feedback From Circadian Variation

Tag Archive for: hpt axis

Enclomiphene and LH/FSH Modulation: Exploring Non-Steroidal Approaches in Male Hormone Research

Enclomiphene and LH/FSH Modulation: Exploring Non-Steroidal Approaches in Male Hormone Research

July 12, 2026/0 Comments/by Pure Tested

Nearly 40% of men over age 45 show some degree of testosterone deficiency, yet conventional testosterone replacement therapy carries a well-documented trade-off: it suppresses the very hormonal signals needed for sperm production. Research into enclomiphene and LH/FSH modulation: exploring non-steroidal approaches in male hormone research has opened a compelling alternative pathway, one that works with the body's own feedback systems rather than overriding them.

Key Takeaways

  • Enclomiphene is the active trans-isomer of clomiphene citrate and functions as a selective estrogen receptor modulator (serm) at the hypothalamus and pituitary.
  • By blocking estrogen receptors upstream, enclomiphene increases GnRH pulse frequency, which drives measurable rises in both LH and FSH.
  • Unlike exogenous testosterone, enclomiphene preserves and may enhance spermatogenesis during treatment.
  • Clinical data show comparable testosterone and gonadotropin increases between enclomiphene and clomiphene over 12 months, with enclomiphene offering a cleaner pharmacological profile.
  • As of 2026, enclomiphene is not FDA-approved as a standalone agent but is accessible through compounding pharmacies for research and clinical use.

Key Takeaways

How Enclomiphene Modulates LH and FSH at the Receptor Level

Clomiphene citrate is a mixture of two geometric isomers: enclomiphene (trans) and zuclomiphene (cis). Research has clarified that the trans-isomer carries the bulk of the therapeutic activity. Zuclomiphene contributes little to the intended hormonal outcomes and may linger in circulation due to a much longer half-life.

Enclomiphene works by occupying estrogen receptors in the hypothalamus and pituitary gland. Under normal physiology, circulating estradiol binds those receptors and signals the brain to reduce gonadotropin-releasing hormone (GnRH) output. When enclomiphene occupies those same receptors without activating them, the brain interprets the signal as low estrogen and responds by increasing GnRH pulse frequency.

That upstream change produces a cascade:

  • GnRH rises – pulsatile release from the hypothalamus intensifies
  • LH surges – the pituitary releases more luteinizing hormone
  • FSH increases – follicle-stimulating hormone output also climbs
  • Testosterone rises – Leydig cells in the testes respond to elevated LH by producing more endogenous testosterone
  • Spermatogenesis continues – Sertoli cells, driven by FSH, maintain sperm production

This mechanism is fundamentally different from exogenous testosterone, which suppresses the HPT axis through negative feedback. Enclomiphene's half-life of roughly 10 hours supports once-daily oral dosing, typically in the 12.5 to 25 mg range, making it a practical research candidate.

Researchers exploring related peptide-based hormonal pathways may also find value in reviewing IPA serm stack research and the broader context of metabolic modulation research lines when designing multi-axis studies.


How Enclomiphene Modulates LH and FSH at the Receptor Level

Clinical Evidence Supporting Enclomiphene and LH/FSH Modulation

A randomized phase II clinical trial demonstrated that enclomiphene citrate produced meaningful increases in morning serum testosterone, estradiol, and LH in men with secondary hypogonadism. Critically, sperm counts remained within the normal range throughout the study period, while men using topical testosterone experienced a marked reduction in spermatogenesis.

A longer comparative study published in 2024 found that enclomiphene and clomiphene produced similar increases in testosterone, estradiol, FSH, and LH over 12 months. That finding is significant because it validates enclomiphene's efficacy while highlighting its advantage: the absence of the zuclomiphene isomer means a cleaner pharmacokinetic profile and potentially fewer off-target effects.

Parameter Enclomiphene Topical Testosterone
LH levels Increased Suppressed
FSH levels Increased Suppressed
Sperm count Maintained Reduced
Endogenous T production Stimulated Replaced

Who is an ideal research candidate? Men with secondary hypogonadism whose testes retain the capacity to respond to LH stimulation represent the most relevant study population. Their HPT axis is intact but under-stimulated, making serm-based intervention a logical research target.

Those investigating broader hormonal and recovery research may find useful context in BPC-157 research themes and TB-500 muscle recovery research, as tissue-level recovery often intersects with hormonal optimization in research models.


Clinical Evidence Supporting Enclomiphene and LH/FSH Modulation

Regulatory Context and Future Research Directions

As of 2026, enclomiphene is not FDA-approved as a standalone therapeutic agent. It remains available through compounding pharmacies, which has shaped how researchers and clinicians access it. Experts in the field have noted that the compound warrants further prospective evaluation given its favorable gonadotropin profile and fertility-preserving properties.

The broader landscape of non-steroidal approaches in male hormone research continues to expand. Researchers are increasingly interested in how serms like enclomiphene interact with other signaling pathways, including those modulated by peptides targeting the growth hormone axis. Resources such as what is new in peptide research and the serm product research page offer additional context for those mapping intersecting research domains.

Parallel interest in mitochondrial and cellular longevity pathways, such as those explored in MOTS-c mitochondrial research and GHK-Cu longevity research themes, reflects a growing recognition that male hormonal health does not exist in isolation.


Conclusion

Research into enclomiphene and LH/FSH modulation: exploring non-steroidal approaches in male hormone research has produced a compelling body of evidence. By selectively blocking estrogen receptors at the hypothalamus and pituitary, enclomiphene amplifies the body's own GnRH-LH-FSH cascade, raises endogenous testosterone, and preserves fertility in a way that exogenous testosterone cannot.

Actionable next steps for researchers and clinicians in 2026:

  1. Review available phase II and comparative trial data to understand the gonadotropin response profile across different dosing windows.
  2. Consider enclomiphene's pharmacokinetics (half-life approximately 10 hours, oral dosing 12.5-25 mg daily) when designing study protocols.
  3. Evaluate patient or subject suitability based on intact HPT axis function and fertility preservation goals.
  4. Monitor LH, FSH, testosterone, estradiol, and sperm concentration as primary outcome markers.
  5. Stay current with regulatory developments, as the compounding pharmacy pathway may evolve.

The non-steroidal serm approach represents one of the most mechanistically precise tools available in male hormone research today.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/enclomiphene-and-lh-fsh-modulation-exploring-non-steroidal-approaches-in-male-ho.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-12 13:17:402026-07-20 15:00:14Enclomiphene and LH/FSH Modulation: Exploring Non-Steroidal Approaches in Male Hormone Research
Enclomiphene: A Selective Estrogen Receptor Modulator (serm) for Male Reproductive Health Research

Enclomiphene: A Selective Estrogen Receptor Modulator (serm) for Male Reproductive Health Research

June 30, 2026/0 Comments/by Pure Tested

Testosterone levels in men have declined by roughly 1% per year since the 1980s, yet testosterone replacement therapy (TRT) — the most common intervention — suppresses the very hormonal axis it aims to support. That paradox has pushed researchers toward a different class of compounds. Enclomiphene: A Selective Estrogen Receptor Modulator (serm) for Male Reproductive Health Research represents one of the most studied alternatives, offering a mechanism that stimulates endogenous testosterone production rather than replacing it externally.

Key Takeaways

  • Enclomiphene is the trans-isomer of clomiphene citrate and works by blocking estrogen receptors at the hypothalamus, stimulating the HPT axis.
  • Research shows enclomiphene produces significantly lower estradiol increases compared to clomiphene, reducing common side effects.
  • Unlike TRT, enclomiphene preserves and may enhance spermatogenesis, making it relevant for fertility-focused research.
  • Enclomiphene significantly increased FSH, LH, and total motile sperm count in clinical studies where clomiphene did not.
  • As of 2026, enclomiphene is not FDA-approved as a standalone agent but is accessible through compounding pharmacies for research contexts.

Mechanism of Action: How Enclomiphene Differs From Other serms

Mechanism of Action: How Enclomiphene Differs From Other serms

Clomiphene citrate is a mixture of two geometric isomers: zuclomiphene (the cis-isomer) and enclomiphene (the trans-isomer). These two isomers behave very differently in the body. Zuclomiphene has weak estrogenic activity and a long half-life, while enclomiphene acts as a pure estrogen receptor antagonist with a shorter half-life and cleaner pharmacokinetic profile.

Enclomiphene works by binding to estrogen receptors in the hypothalamus, blocking the normal negative feedback signal that estrogen sends to the brain. When estrogen can no longer signal "enough hormone is present," the hypothalamus releases more gonadotropin-releasing hormone (GnRH). This triggers the pituitary gland to secrete luteinizing hormone (LH) and follicle-stimulating hormone (FSH), which in turn stimulate the testes to produce testosterone and support sperm production.

This is the key distinction from TRT. Testosterone replacement shuts down the hypothalamic-pituitary-testicular (HPT) axis through negative feedback, suppressing LH and FSH and leading to testicular atrophy and infertility. Enclomiphene does the opposite — it amplifies the axis rather than bypassing it.

"Enclomiphene stimulates the body's own testosterone production pathway, preserving the hormonal architecture that TRT dismantles."

For researchers exploring compounds that interact with the endocrine system, understanding this axis is foundational. Related research on neuroendocrine and innate immunity interactions provides useful context for how hormonal signaling intersects with broader physiological systems.


Clinical Research Findings: Enclomiphene as a serm in Male Reproductive Studies

Research comparing enclomiphene directly to clomiphene has produced several meaningful findings.

Testosterone and Estradiol Outcomes

A study involving 66 hypogonadal men found that enclomiphene produced a median testosterone increase of 166 ng/dL compared to 98 ng/dL with clomiphene. While this difference was not statistically significant (P=0.20), the estradiol data was striking. Enclomiphene resulted in a statistically significant lower increase in estradiol levels compared to clomiphene (−5.92 vs. +17.50 pg/mL, P=0.001).

This estradiol difference matters clinically. Elevated estradiol in men is associated with gynecomastia, mood changes, and reduced libido — all common complaints with clomiphene use.

Adverse Effect Profile

The same study found that patients on enclomiphene reported significantly fewer adverse effects:

Adverse Effect Enclomiphene Clomiphene P-value
Decreased libido Lower incidence Higher incidence 0.001
Reduced energy Lower incidence Higher incidence 0.044
Mood changes Lower incidence Higher incidence 0.030

Sperm Parameters and Gonadotropins

A 2023 retrospective study of 78 men found that enclomiphene produced a statistically significant increase in total motile sperm count (TMSC), while clomiphene did not. Enclomiphene also significantly raised both FSH and LH levels — critical markers of HPT axis activation — whereas clomiphene again showed no significant effect on these gonadotropins.

These findings position enclomiphene as a particularly relevant compound for secondary hypogonadism research in younger men who wish to maintain fertility.

Researchers studying related peptide compounds that influence body composition and hormonal balance may find value in reviewing ipamorelin research on muscle and fat metabolism as a complementary area of inquiry.


Research Context, Safety Profile, and Future Directions

Research Context, Safety Profile, and Future Directions

As of 2026, enclomiphene is not FDA-approved as a single-agent therapy in the United States. It is available through compounding pharmacies and is used in research contexts examining secondary hypogonadism, male infertility, and alternatives to TRT.

Its safety profile in current research appears favorable compared to clomiphene, largely due to the absence of the estrogenic zuclomiphene isomer. This cleaner receptor selectivity makes it a useful research model for understanding how pure estrogen receptor antagonism affects the male HPT axis.

Researchers working with serms and related compounds should also consider how other research-grade compounds interact with hormonal and metabolic pathways. For example, PT-141 research in central arousal pathways explores a separate but related dimension of male reproductive health at the neuroendocrine level. Similarly, GLP-1 and incretin research themes highlight how metabolic signaling intersects with hormonal health in male subjects.

For those sourcing research-grade serms, verified compound quality is essential. Reviewing available certificates of analysis and sourcing from suppliers with documented purity testing ensures research integrity. Those specifically looking for serm compounds for research purposes can explore the serm 10mg research compound as a starting reference point.


Conclusion

Enclomiphene: A Selective Estrogen Receptor Modulator (serm) for Male Reproductive Health Research occupies a unique position in endocrinology research. Its targeted mechanism — blocking hypothalamic estrogen receptors to amplify the HPT axis — produces measurable increases in LH, FSH, testosterone, and total motile sperm count, while generating significantly less estrogenic activity than its parent compound, clomiphene.

Actionable next steps for researchers:

  • Review published clinical comparisons between enclomiphene and clomiphene for HPT axis endpoint data.
  • Evaluate estradiol and gonadotropin panels as primary outcome markers in any serm-related male reproductive study design.
  • Source compounds exclusively from suppliers providing third-party purity verification and documented certificates of analysis.
  • Consider enclomiphene alongside complementary research areas such as peptide-based hormonal modulation for a broader picture of male endocrine health.

The research landscape in 2026 continues to support enclomiphene as a compound of significant scientific interest for male reproductive and hormonal health studies.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Enclomiphene-A-Selective-Estrogen-Receptor-Modulator-serm-for-Male-Reproductive-Health-Research.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-30 13:18:122026-07-20 15:01:53Enclomiphene: A Selective Estrogen Receptor Modulator (serm) for Male Reproductive Health Research
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top