

Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models
Selective COX-2 inhibition reduces myofiber cross-sectional area by up to 33% during the first three weeks after muscle injury, a finding that challenges the routine use of NSAIDs like meloxicam in early musculoskeletal recovery. This single data point captures the central tension explored in Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models: two fundamentally different pharmacological strategies, one aimed at quieting inflammation and one aimed at rebuilding tissue, produce strikingly different outcomes at the cellular level.
Key Takeaways
- Meloxicam suppresses COX-2-dependent prostaglandin signaling, which reduces inflammation but may simultaneously impair early tissue regeneration in muscle, bone, and tendon models.
- BPC-157 activates FAK-paxillin, PI3K/Akt, VEGF, and TGF-beta pathways in vitro, supporting fibroblast proliferation, collagen synthesis, and angiogenesis.
- TB-500 promotes actin polymerization, progenitor cell recruitment, and collagen fiber organization through MAPK, NF-kB, and cytoskeletal repair pathways.
- No robust human randomized controlled trials currently compare BPC-157 or TB-500 with meloxicam in musculoskeletal injury; all comparative evidence comes from cell and rodent studies.
- Both peptides remain unapproved, are excluded from FDA compounding lists, and are prohibited under WADA rules, making them strictly research-use compounds as of 2026.
How Meloxicam Works in Tissue-Injury Cell Models
Meloxicam is a COX-2-preferential NSAID with a COX-2:COX-1 IC50 ratio of approximately 0.09 in human whole-blood assays, meaning it inhibits COX-2 at concentrations far below those needed to affect COX-1. This selectivity drives its analgesic and anti-inflammatory profile, but it also places COX-2-dependent regenerative signaling directly in the line of fire.
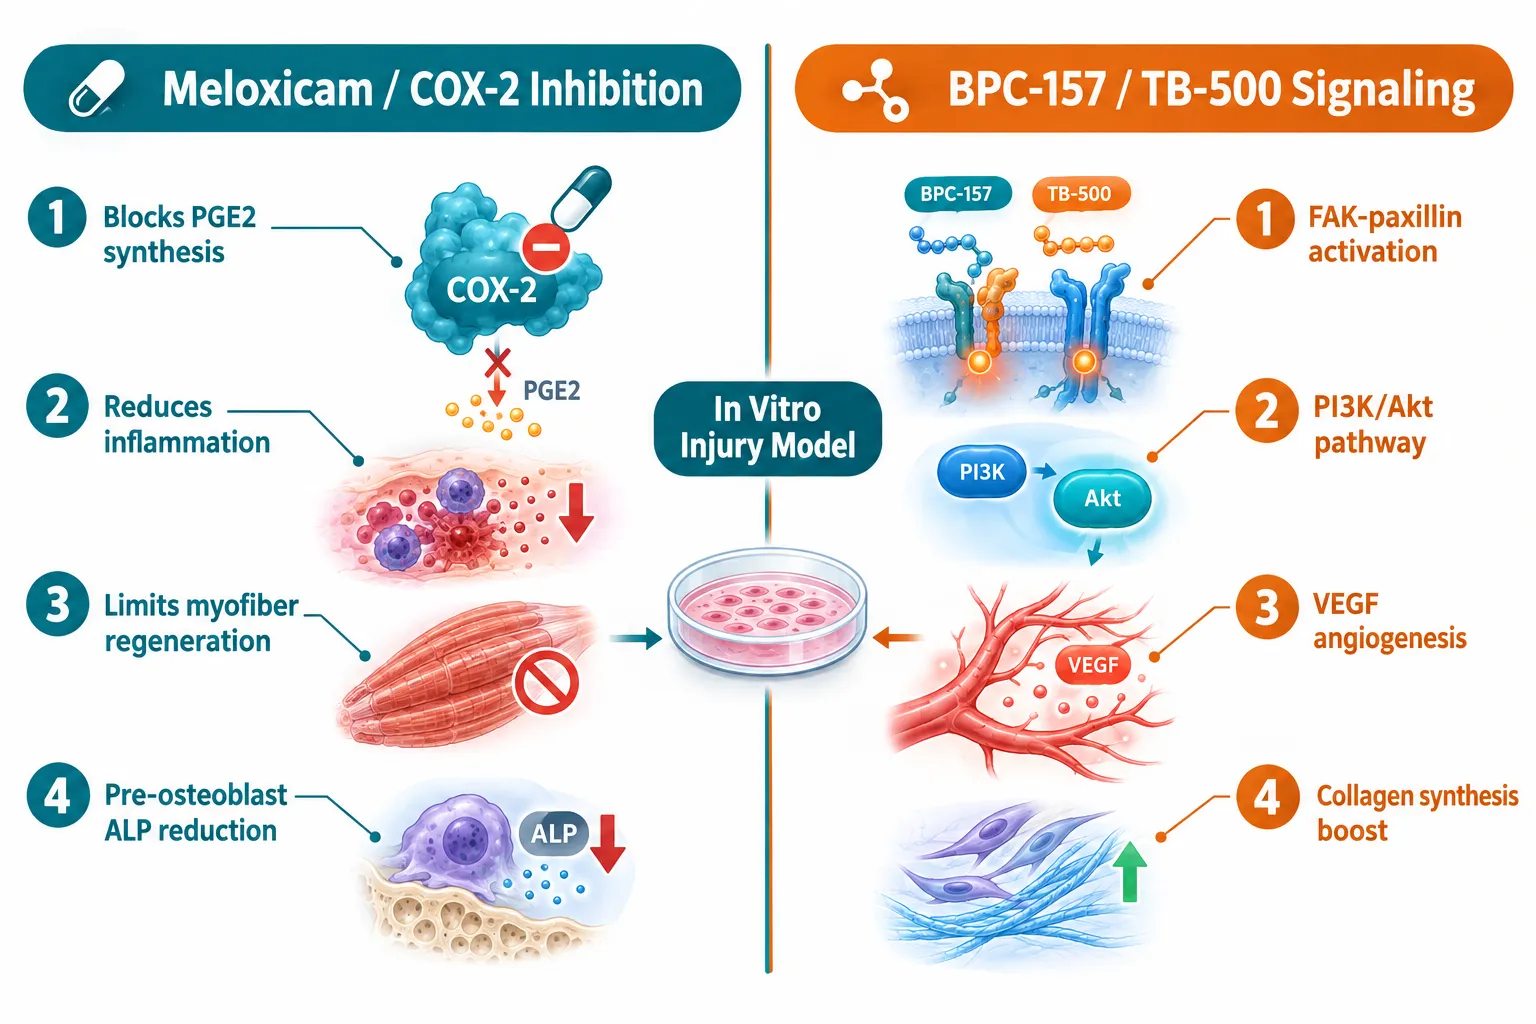
In human Achilles tendon-derived tenocytes exposed to oxidative stress via hydrogen peroxide, 24-hour meloxicam treatment can increase cell metabolic activity relative to untreated controls. At the same time, it consistently reduces prostaglandin E2 (PGE2) production through COX-2 inhibition. This creates a mechanistic paradox: the drug may support short-term cell viability under stress while simultaneously blunting the prostaglandin signals that coordinate early repair cascades.
The downstream consequences vary by tissue type:
- Muscle: COX-2 inhibitors analogous to meloxicam reduce myoblast count and inflammatory cell recruitment, impairing fiber regeneration during the first three weeks post-injury.
- Bone: Preclinical fracture models show impaired healing with COX-2 inhibitors, including meloxicam, and animal tendon-to-bone repair studies report compromised integration compared with acetaminophen controls.
- Cartilage: In osteoarthritic canine chondrocytes, up to 30 days of meloxicam exposure does not increase matrix metalloproteinase production, suggesting the cartilage matrix is relatively preserved.
- Osteogenesis: Meloxicam reduces alkaline phosphatase activity in pre-osteoblasts, yet some selective COX-2 inhibitors leave osteogenic differentiation of human adipose-derived stromal cells unaltered.
"The data on meloxicam in musculoskeletal cell models are mechanistically coherent but contextually mixed, tissue type and injury timing determine whether COX-2 inhibition helps or hinders."
These nuances are directly relevant to researchers designing wound models that use meloxicam as a reference compound.
BPC-157 and TB-500 Signaling in the Same In Vitro Systems
When examining Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models, the peptide side of the comparison reveals a fundamentally different mechanistic profile. Rather than suppressing a single enzymatic pathway, both peptides activate multiple pro-repair cascades simultaneously.
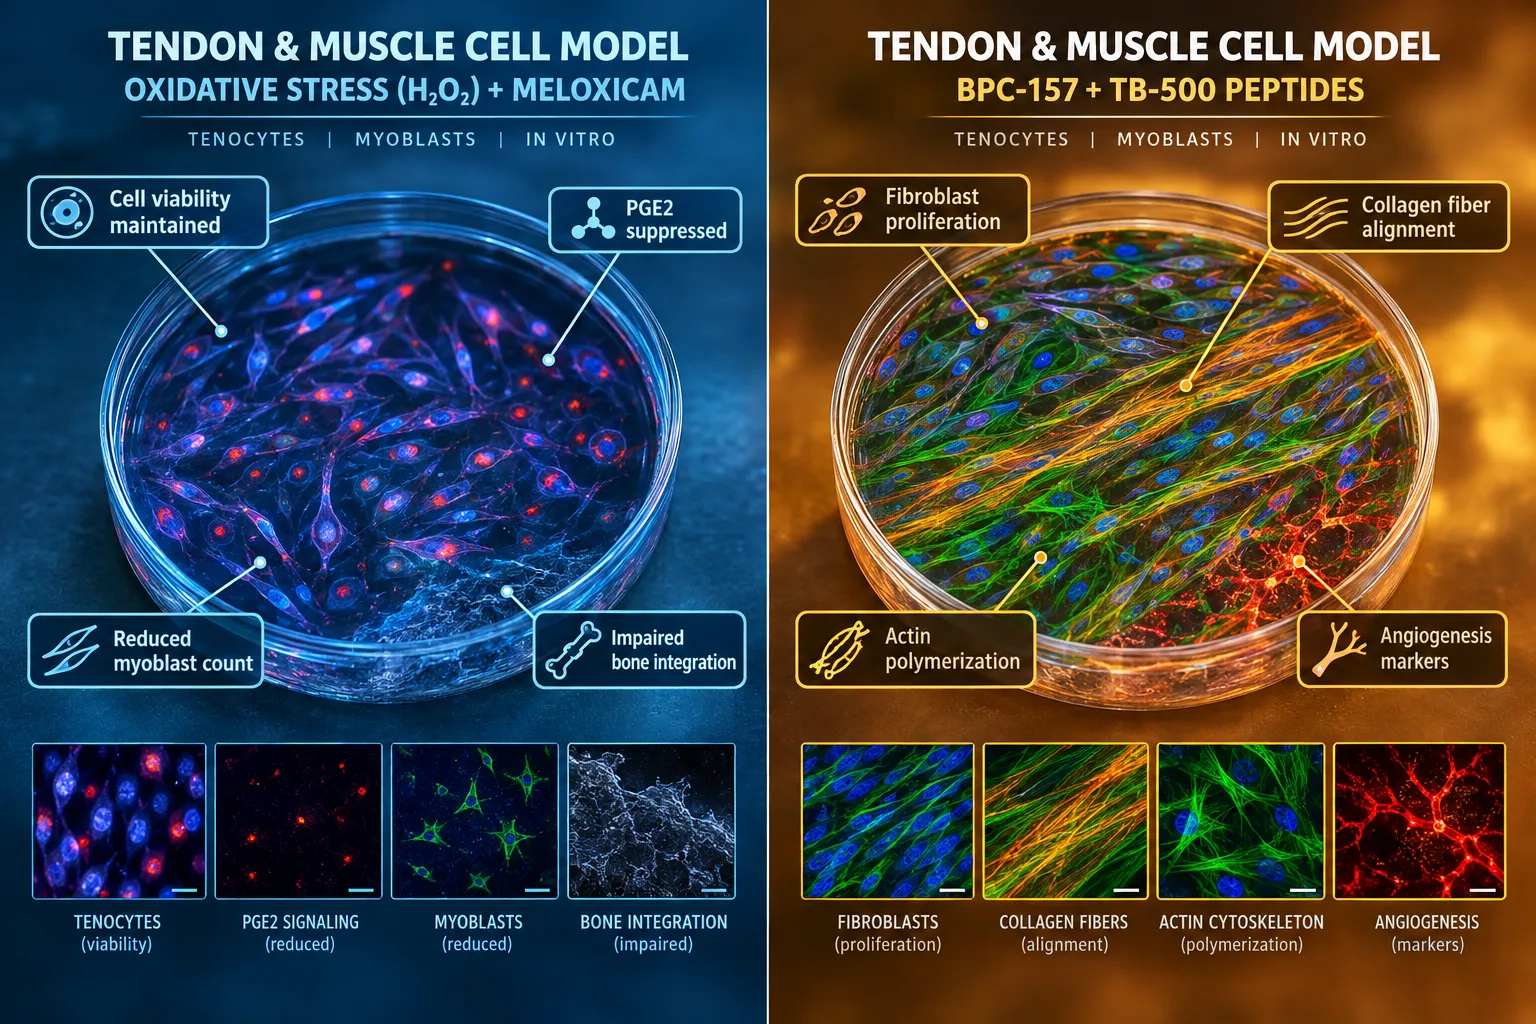
BPC-157 is a 15-amino-acid synthetic peptide with a broad signaling footprint in tendon and ligament models:
- Enhances tendon fibroblast proliferation and collagen synthesis
- Activates focal adhesion kinase (FAK)-paxillin signaling, rescuing tendocyte growth under oxidative stress
- Upregulates growth hormone receptor expression and signals through PI3K/Akt, VEGF, NO/eNOS, and TGF-beta pathways
- Accelerates tendon explant outgrowth and supports extracellular matrix remodeling
In transected rat Achilles tendon models, BPC-157 improves biomechanical endpoints including failure load and Young's modulus, outcomes that reflect genuine structural repair rather than pain suppression alone.
TB-500, a synthetic fragment of thymosin beta-4, works through complementary but distinct biology:
- Promotes actin polymerization and progenitor cell recruitment
- Enhances cell migration indices in ligament repair models
- Produces more uniform collagen fiber bundles and larger fibril diameters at four weeks
- Activates MAPK, NF-kB, FAK, and cytoskeletal repair pathways alongside pro-angiogenic activity
Researchers exploring these mechanisms can find relevant wound repair peptides and resources on wound repair and wound healing peptides for further context on how these compounds are studied in controlled settings.
A 2023 rat Achilles rupture-repair study found that both BPC-157 and TB-500 improved histopathological organization and extracellular matrix remodeling during early repair. However, direct head-to-head comparisons of both peptides within the same in vitro model remain sparse, and the preponderance of BPC-157 data comes from a single research group.
Regulatory Status, Research Gaps, and Lab Safety Considerations
Understanding Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models requires an honest accounting of where the evidence stands and what the regulatory environment looks like as of 2026.
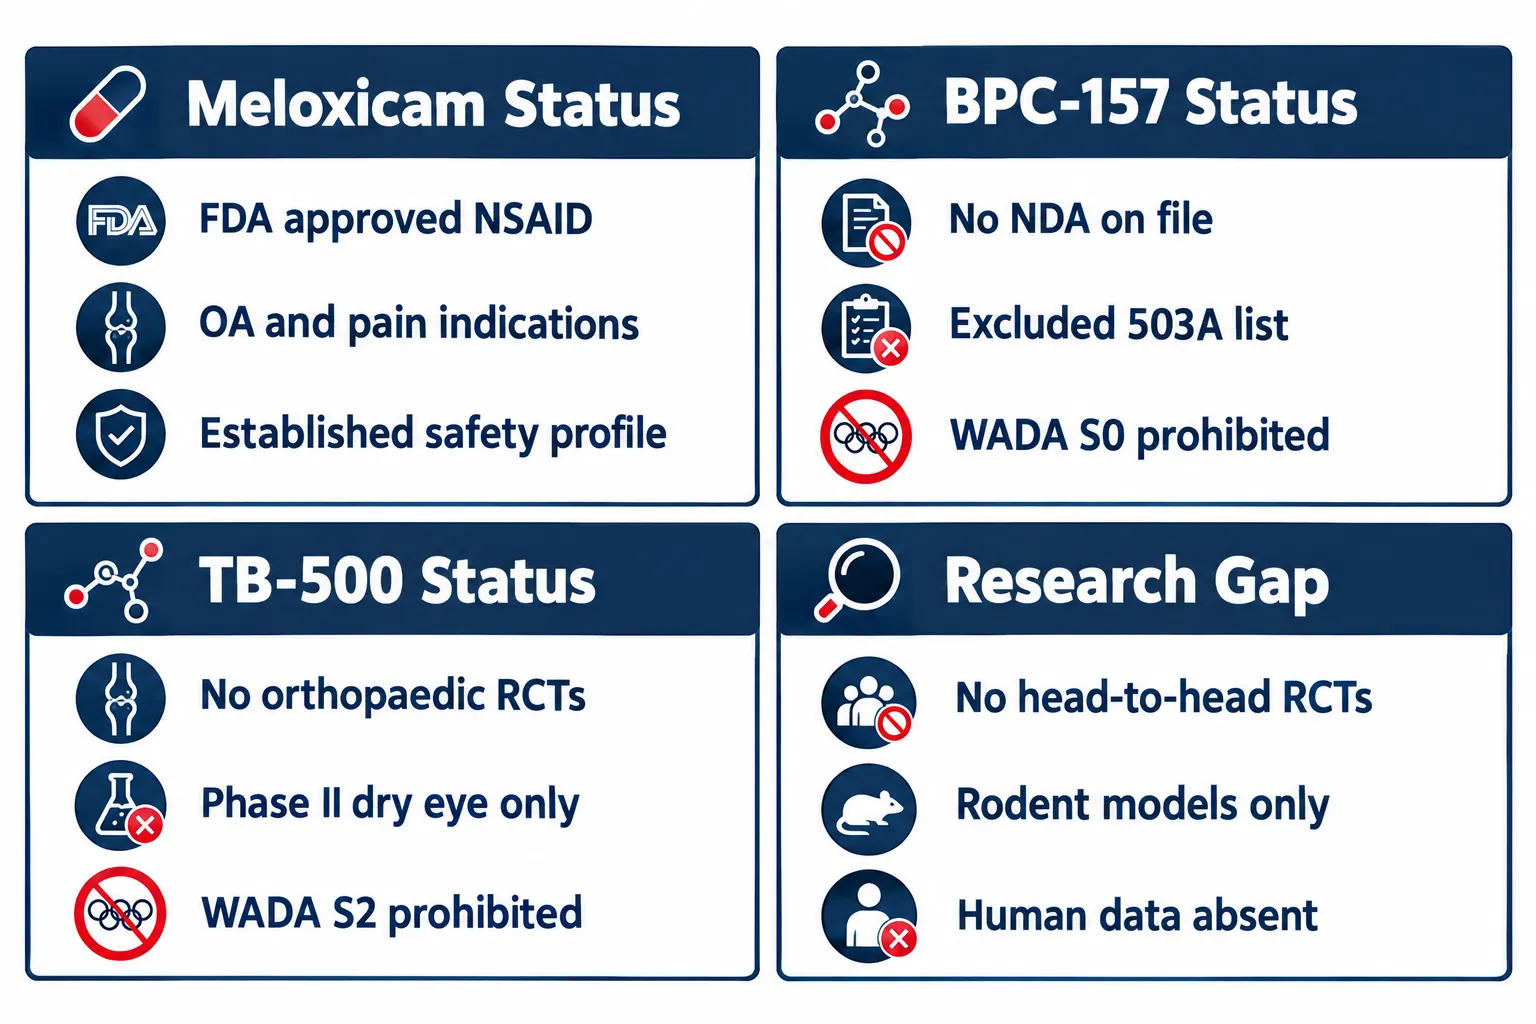
Meloxicam is an established, FDA-approved NSAID with well-characterized pharmacokinetics, approved indications for osteoarthritis and other pain conditions, and decades of human safety data.
BPC-157 and TB-500 occupy a very different position:
| Dimension | Meloxicam | BPC-157 | TB-500 |
|---|---|---|---|
| FDA approval | Yes | No | No |
| Human RCT data (orthopaedic) | Extensive | None | None |
| WADA status | Permitted | S0 prohibited | S2 prohibited |
| 503A compounding | Permitted | Excluded | Excluded |
| Highest-quality evidence | Phase III/IV trials | Rodent + cell studies | Phase II (dry eye only) |
Both peptides have been excluded from the FDA's 503A bulk-drug compounding list, are not listed for 503B outsourcing compounding, and remain unapproved with no New Drug Applications on file. The FDA's Pharmacy Compounding Advisory Committee reviewed both compounds in July 2026 in the context of wound-healing and orthopaedic compounding, but neither has moved to an approved status.
For researchers sourcing compounds for in vitro work, using a best peptide supplier with verified purity documentation is essential. Researchers should also review resources on wholesale peptides for sale to ensure laboratory-grade material is used strictly within approved research protocols.
The only human data for BPC-157 in a musculoskeletal context is a single small case series of 17 patients receiving intra-articular injections for knee tendon and ligament symptoms, a study with significant methodological limitations. TB-500 has completed two Phase II trials, both in dry eye disease, with no orthopaedic RCTs published to date.
Conclusion
The comparison of Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models reveals two pharmacological philosophies operating at opposite ends of the repair spectrum. Meloxicam suppresses a single enzymatic node, COX-2, with well-understood consequences for inflammation and, depending on tissue type and timing, potentially for regeneration itself. BPC-157 and TB-500 activate broad, overlapping pro-repair networks in cell and animal models, producing structural improvements in collagen organization, cell migration, and biomechanical endpoints that no NSAID is designed to achieve.
Actionable next steps for researchers:
- When using meloxicam as a reference NSAID in injury models, account for tissue type, muscle and bone models are more sensitive to COX-2 inhibition than cartilage models.
- Treat BPC-157 and TB-500 data critically: most evidence is rodent-derived, and human orthopaedic outcome data are essentially absent as of 2026.
- Source peptides only from suppliers with verified purity certificates and use them exclusively within approved institutional research frameworks.
- Monitor FDA Pharmacy Compounding Advisory Committee deliberations, as the regulatory status of both peptides remains under active review.
- Design future in vitro studies with direct head-to-head comparisons of NSAID and peptide conditions within the same cell model to generate more translatable mechanistic data.
The mechanistic gap between these compound classes is large and scientifically meaningful. Closing it will require well-designed, independently replicated human trials, work that has not yet been done.