Growth-Hormone Secretagogue Research Design: Comparing Tesamorelin, CJC-1295, Ipamorelin, and Sermorelin by Signal Duration
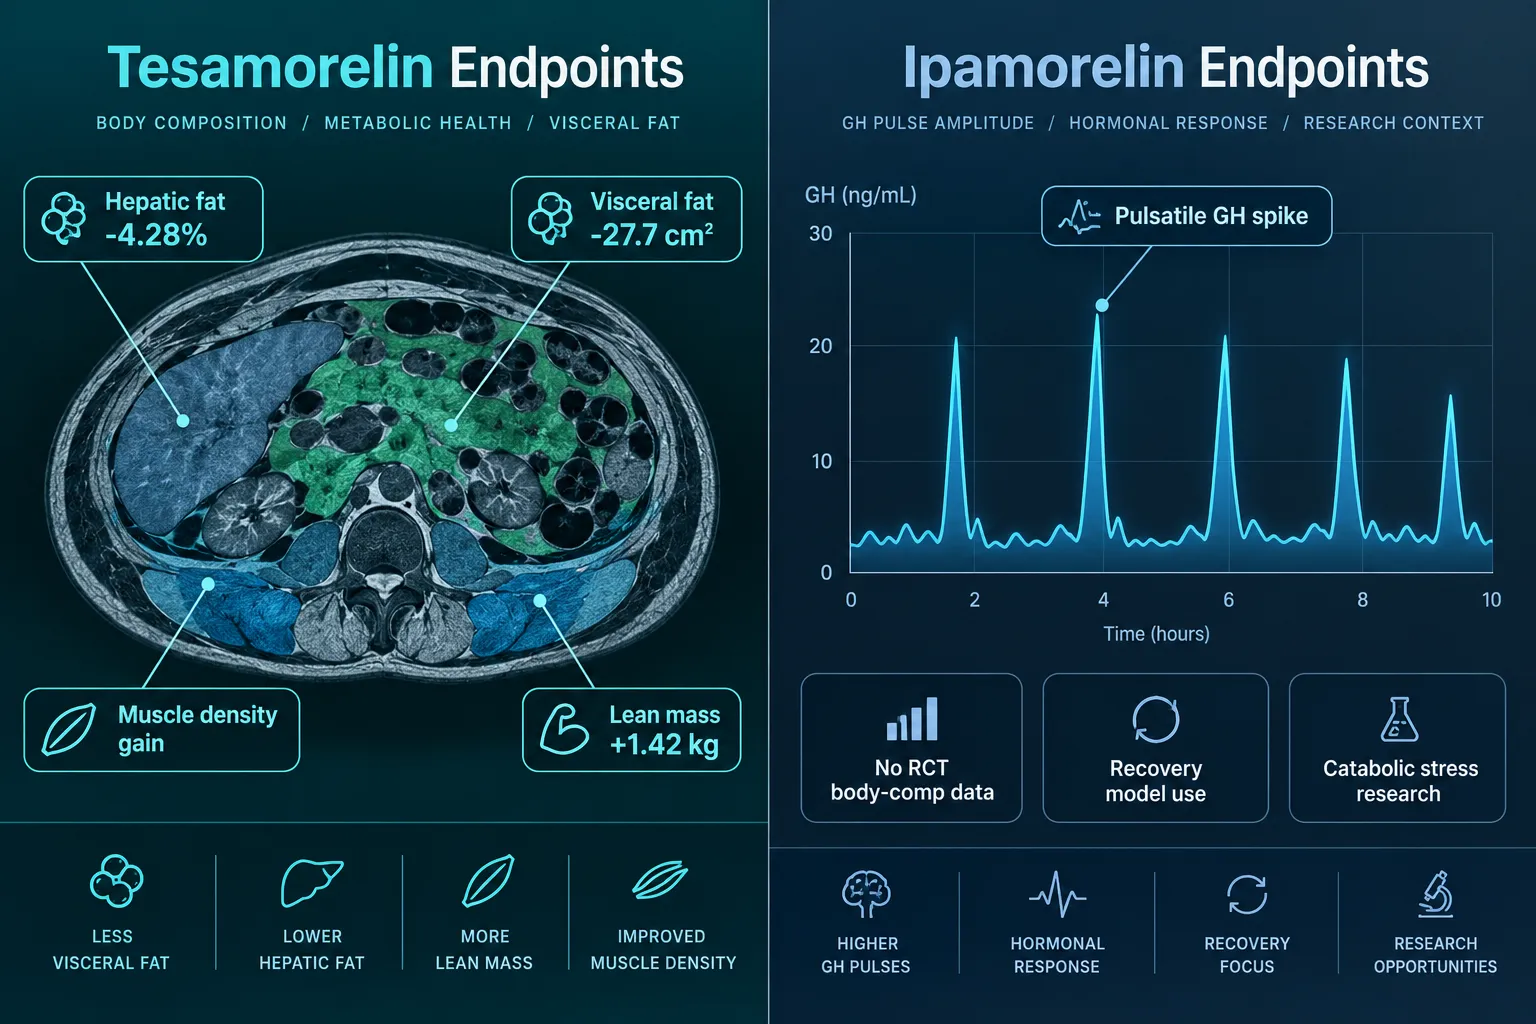
Fewer than 4% of a subcutaneous tesa dose reaches systemic circulation, yet that brief plasma exposure, peaking in under 10 minutes and clearing within roughly half an hour, is enough to drive measurable reductions in visceral fat in HIV-associated lipodystrophy. That pharmacokinetic reality sits at the core of Growth-Hormone Secretagogue Research Design: Comparing Tesamorelin, CJC-1295, Ipamorelin, and Sermorelin by Signal Duration: the duration of a peptide's plasma signal is not a side note, it is the primary variable that determines assay timing, endpoint selection, and the validity of any IGF-1 interpretation.
Key Takeaways
- Tesamorelin and sermorelin are ultra-short GHRH analogs (half-lives of roughly 11-38 minutes and 10-12 minutes, respectively); assay windows must open within minutes of dosing.
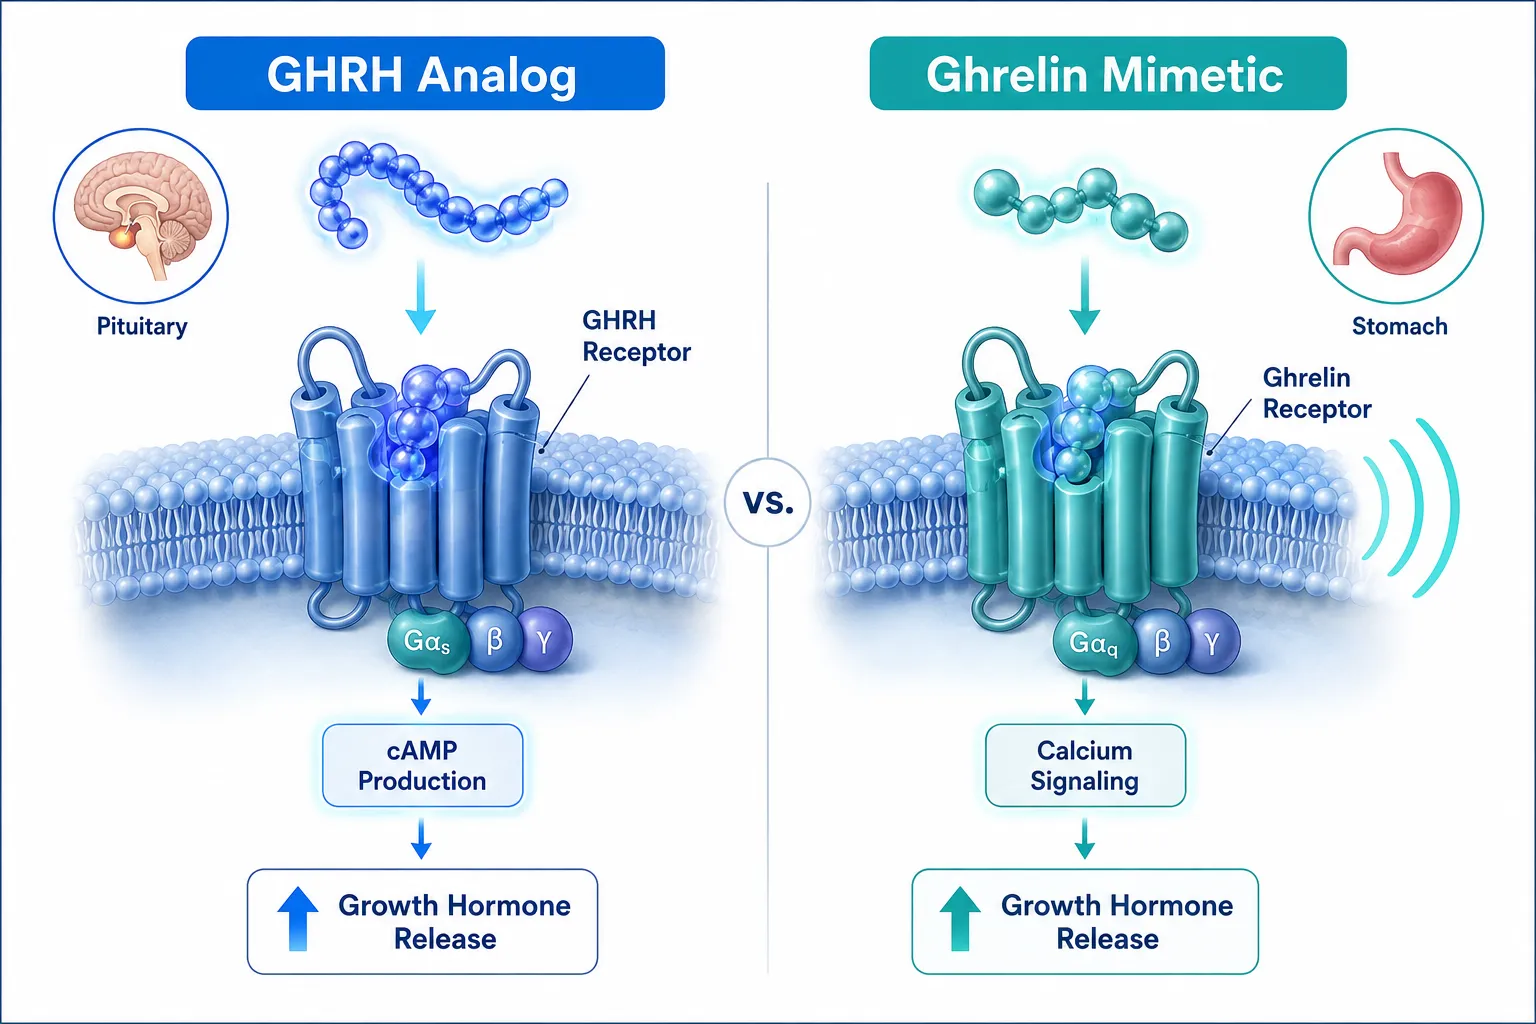
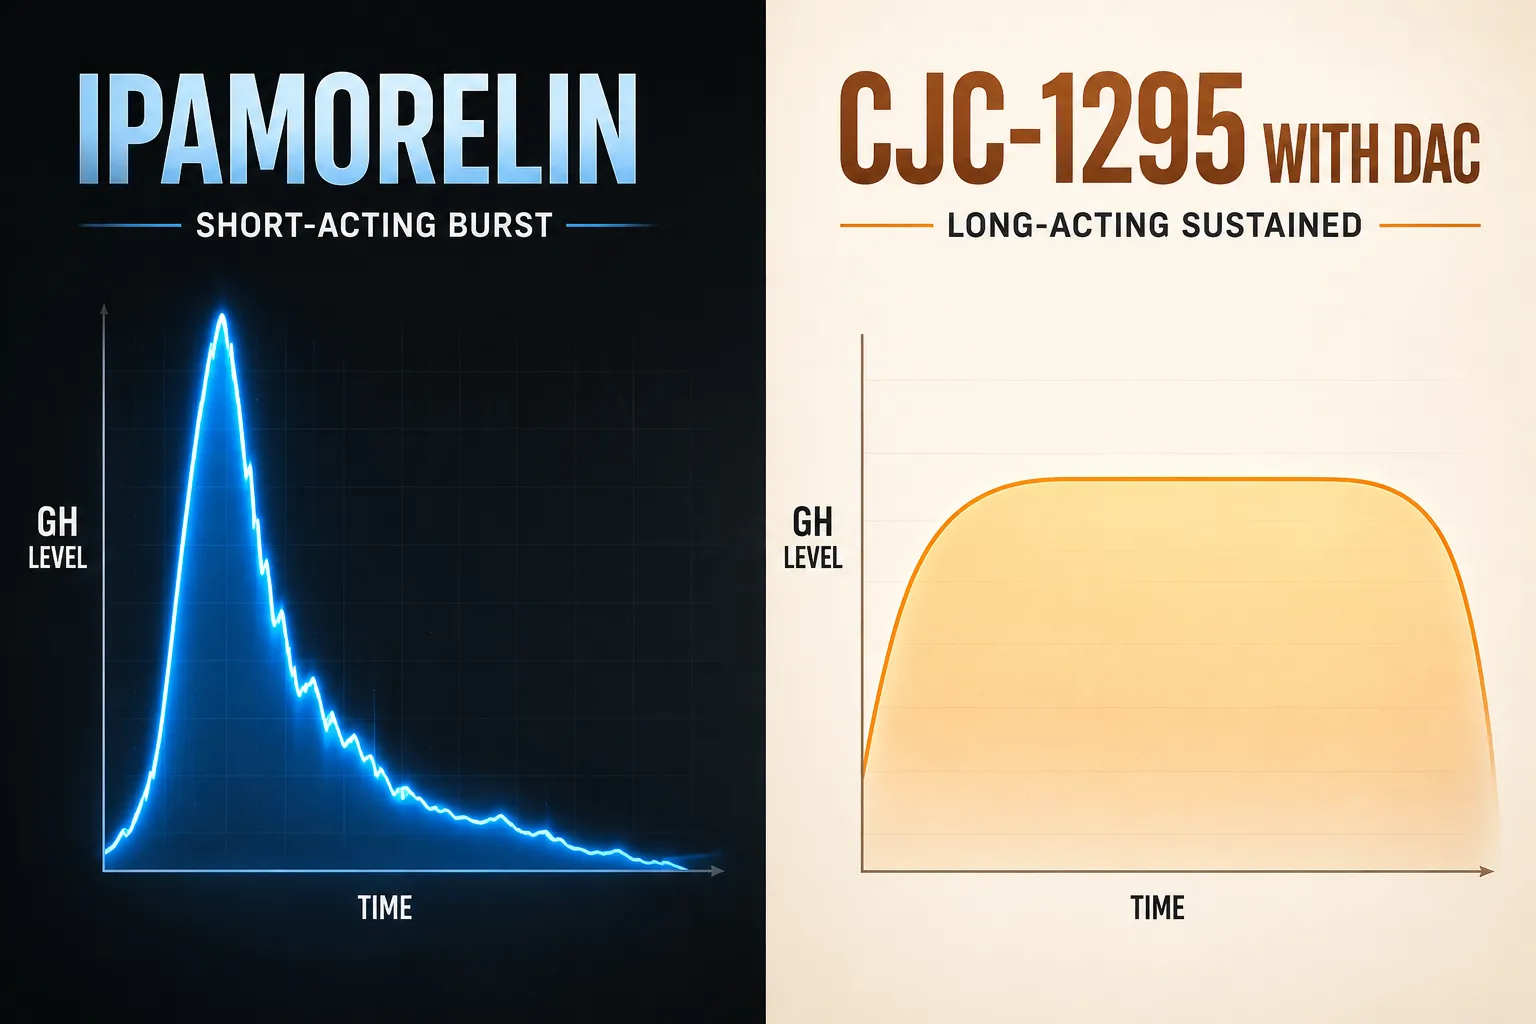
- Ipamorelin acts at a different receptor (GHS-R1a, not the GHRH receptor), carries an approximately 2-hour half-life, and generates a longer but still transient GH pulse.
- CJC-1295 with DAC is a depot GHRH analog with a half-life of 5.8-8.1 days; it converts a single injection into a week-long endocrine signal, which fundamentally changes the experimental question.
- DAC status is a design-level variable for CJC-1295 studies, without DAC, the half-life collapses to minutes; with DAC, it extends to days.
- No completed human randomized trial has evaluated the CJC-1295 plus ipamorelin combination, so signal-duration synergy claims remain extrapolated from single-agent data.
Pulse Architecture: How Signal Duration Defines the Experiment
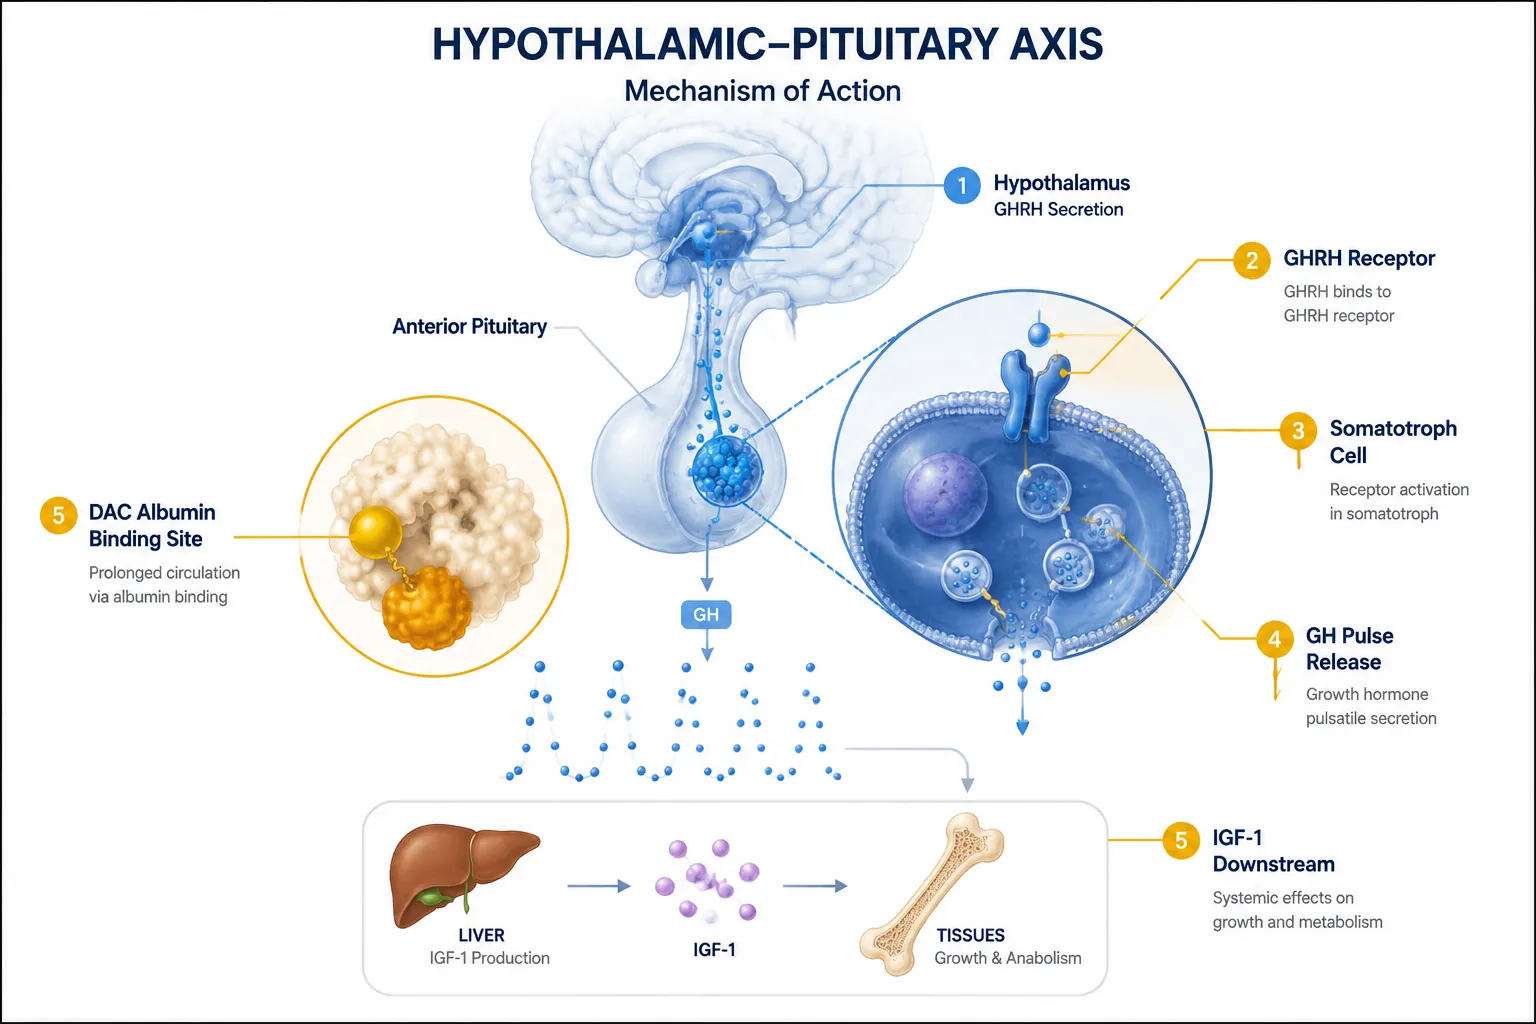
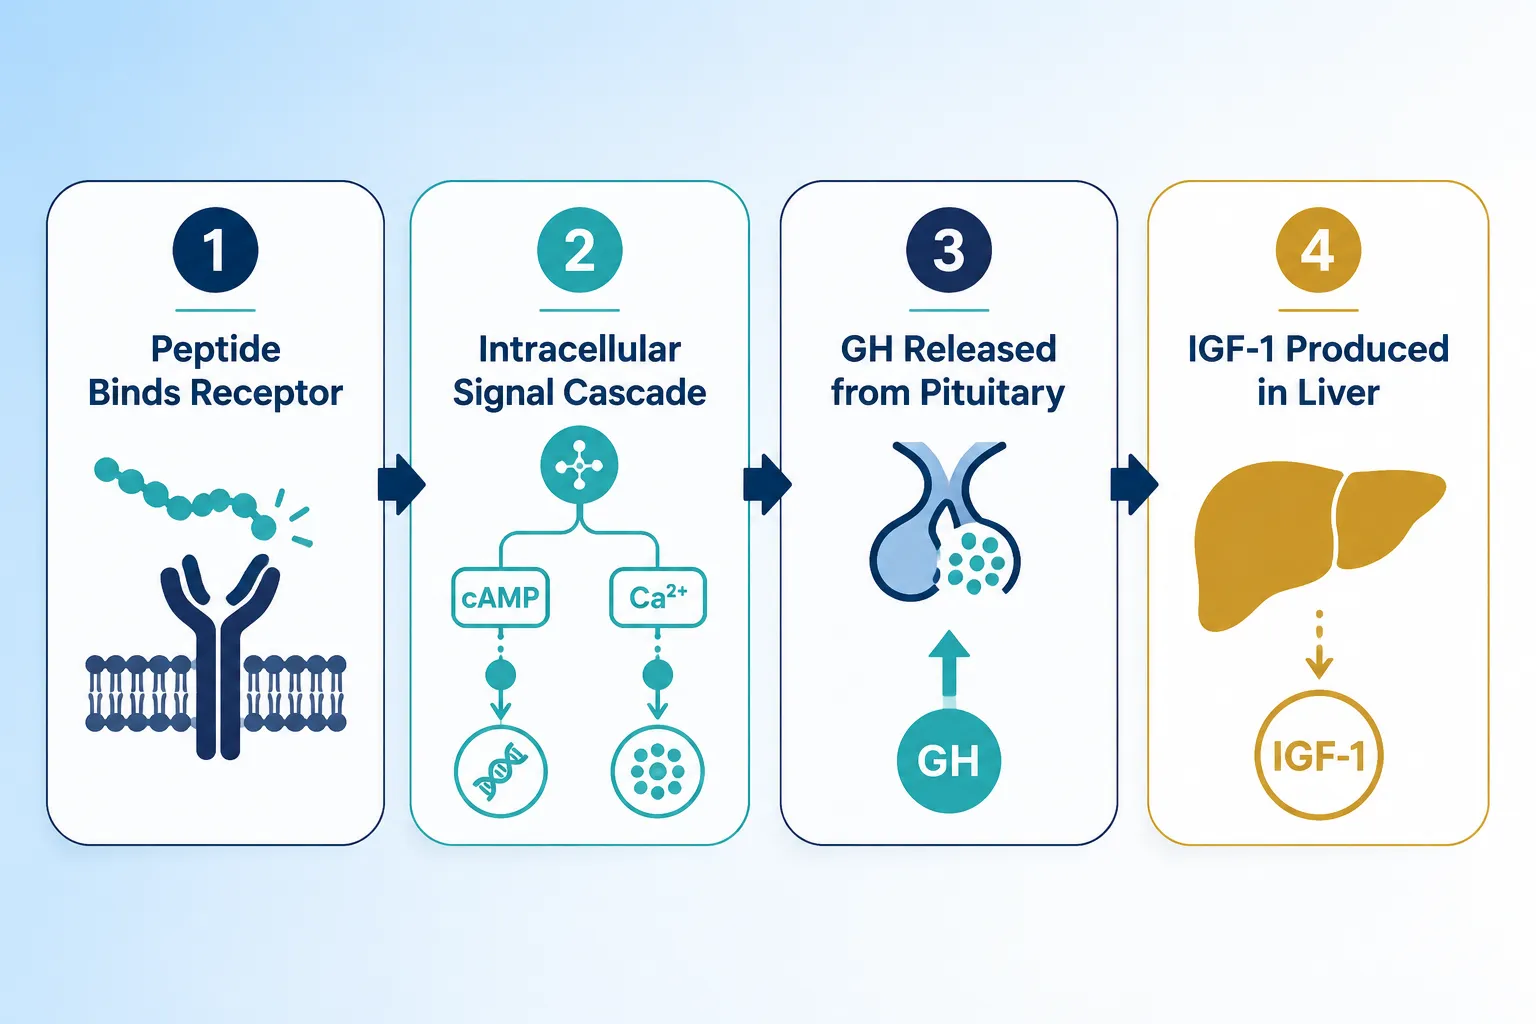
Every GH secretagogue study is, at its foundation, a study of pulse architecture. The hypothalamic-pituitary axis releases GH in discrete bursts. Secretagogues either mimic or amplify those bursts. The key question for research design is: how long does the secretagogue's plasma signal last, and what does that mean for when you measure?
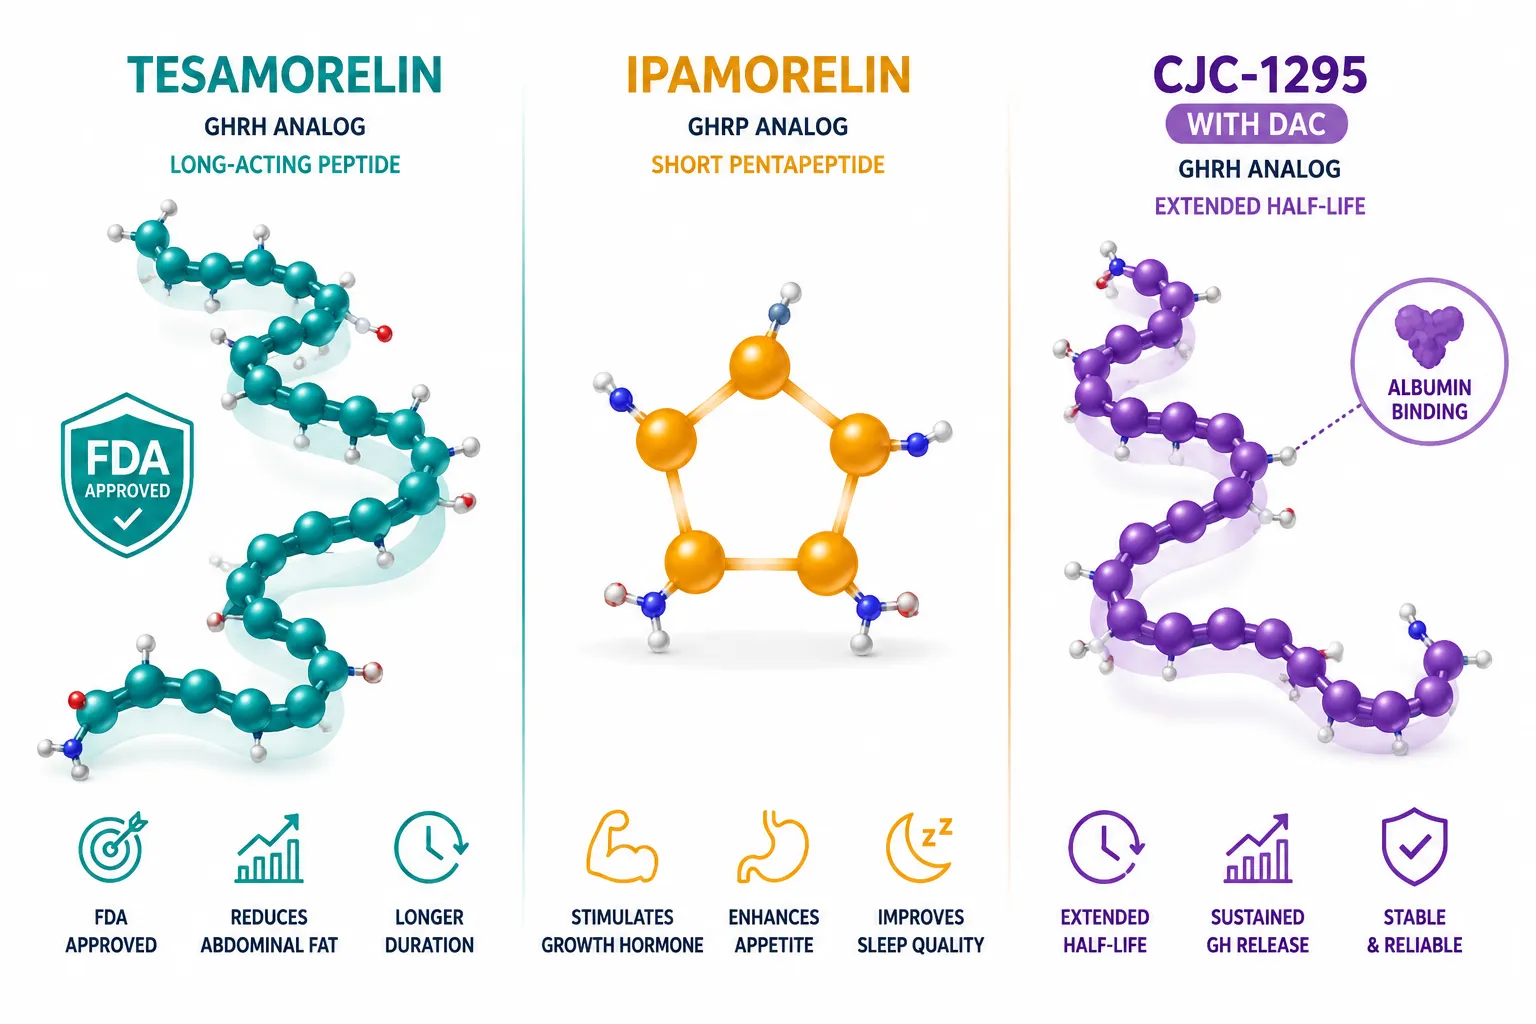
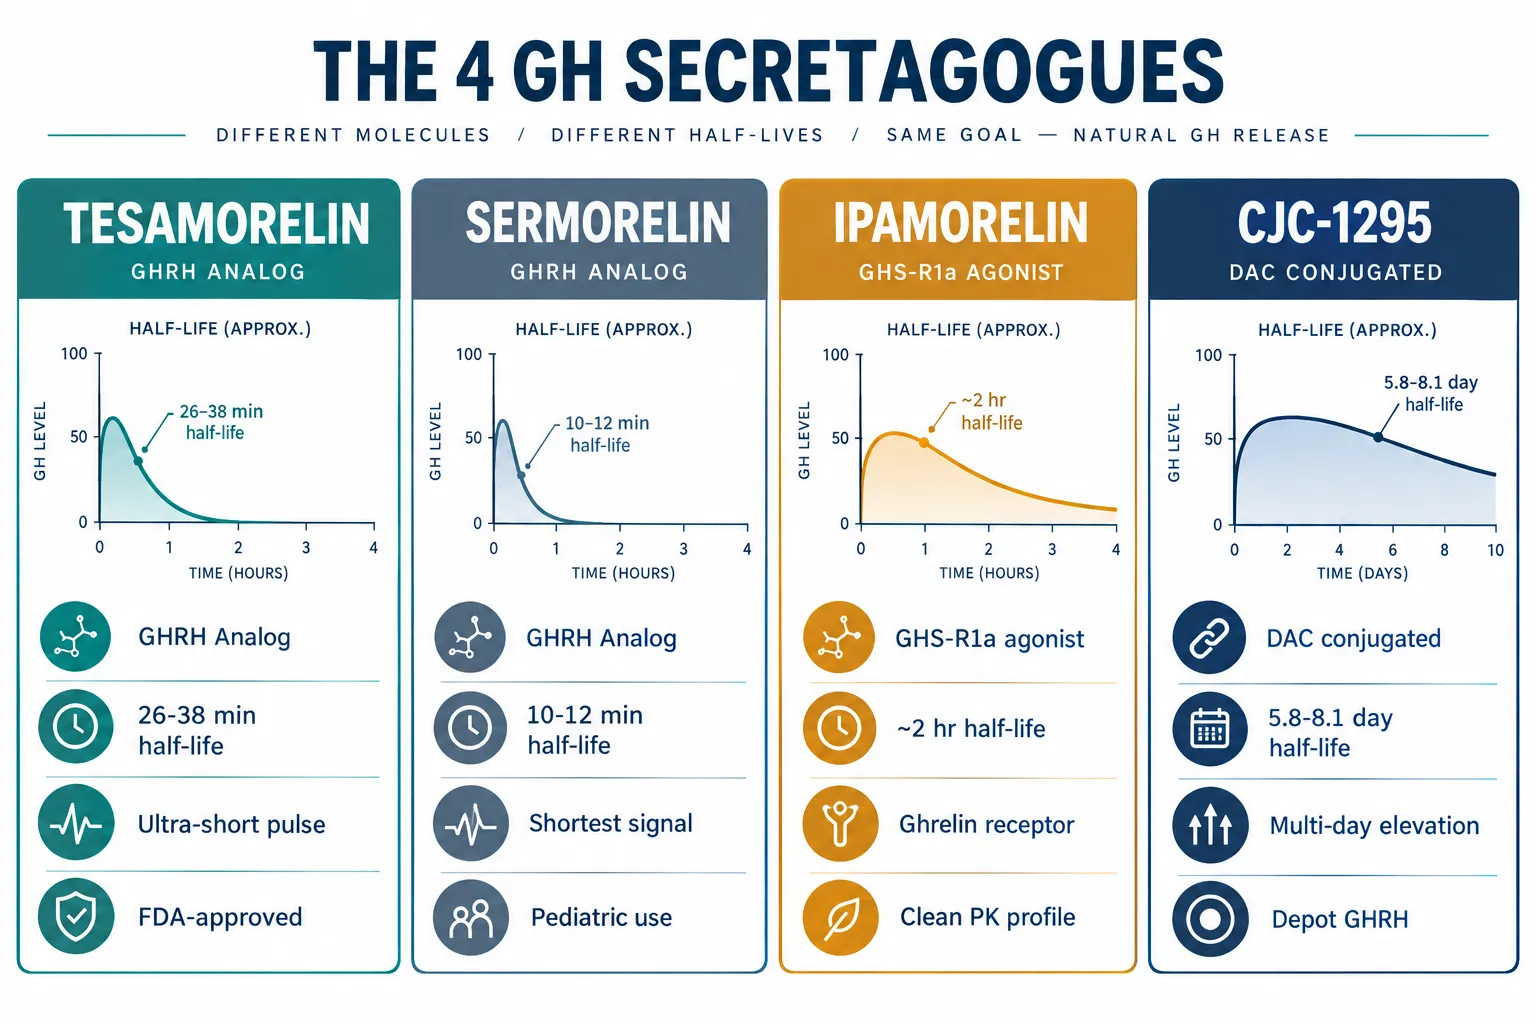
The four agents in this comparison span roughly four orders of magnitude in signal duration:
| Agent | Receptor Target | Approximate Half-Life | Signal Category |
|---|---|---|---|
| Sermorelin | GHRH receptor | 10-12 minutes | Ultra-short |
| Tesamorelin | GHRH receptor | 11-38 minutes | Ultra-short |
| Ipamorelin | GHS-R1a (ghrelin receptor) | ~2 hours | Short |
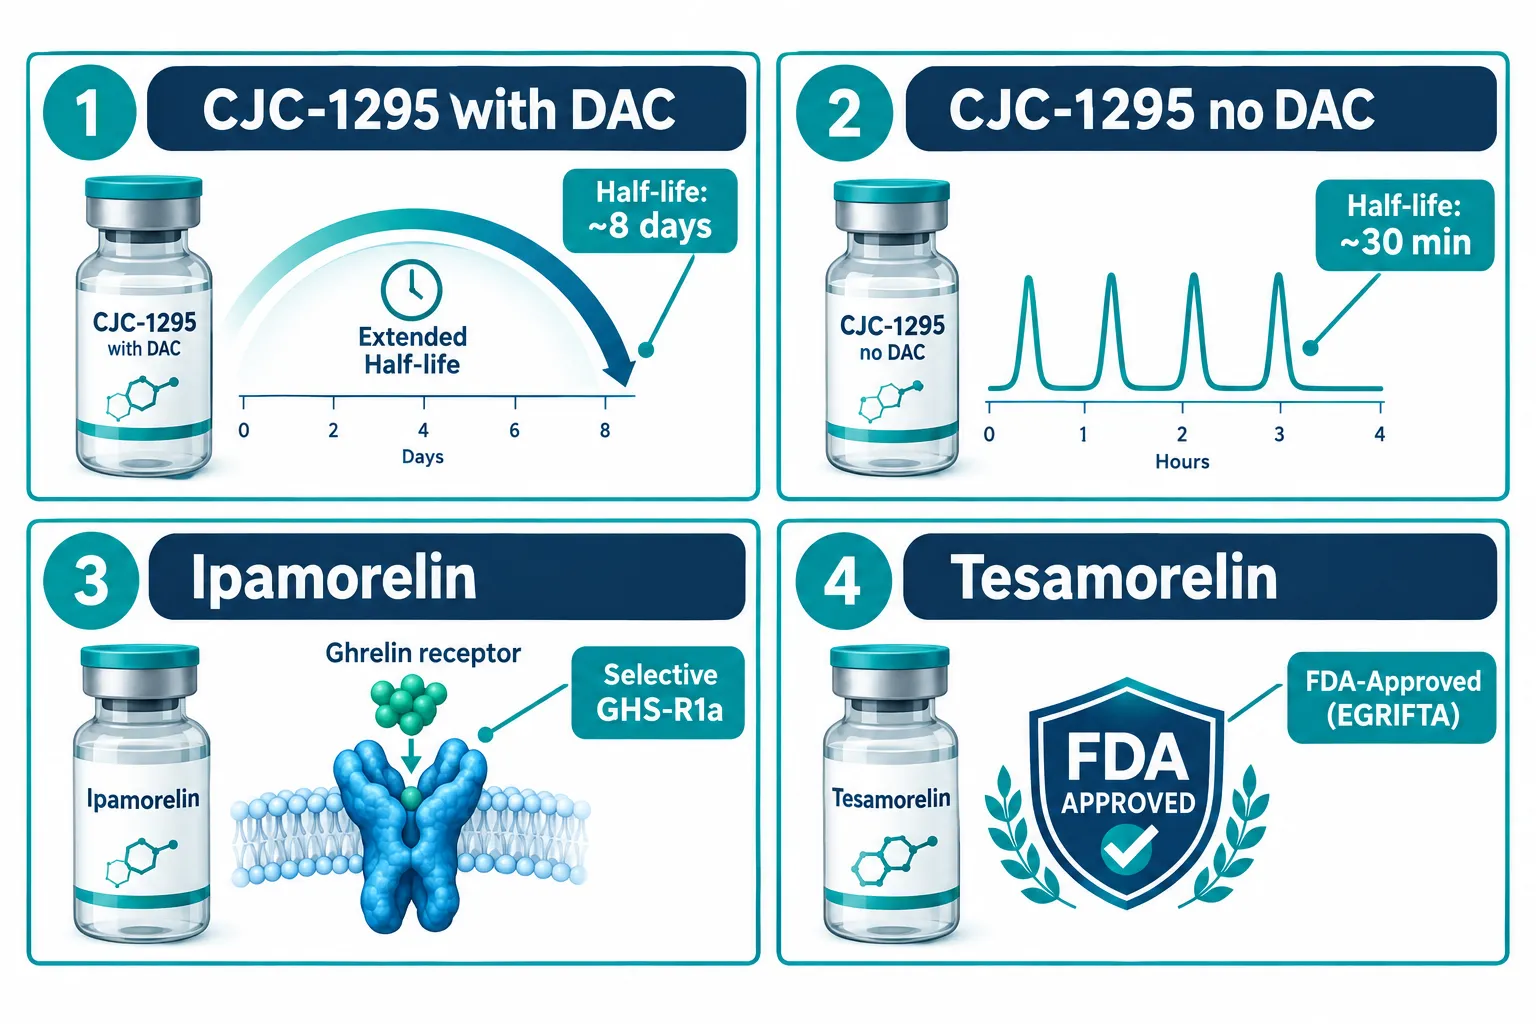
| CJC-1295 with DAC | GHRH receptor | 5.8-8.1 days | Long (depot) |
Sermorelin is a truncated GHRH analog. Its plasma half-life of roughly 10-12 minutes means a GH pulse is triggered almost immediately after injection, and the secretagogue itself is largely cleared before most clinical blood draws are even processed. Sermorelin remains primarily used in pediatric growth hormone deficiency contexts and carries no FDA approval for adult indications, which limits the pool of controlled adult trial data.
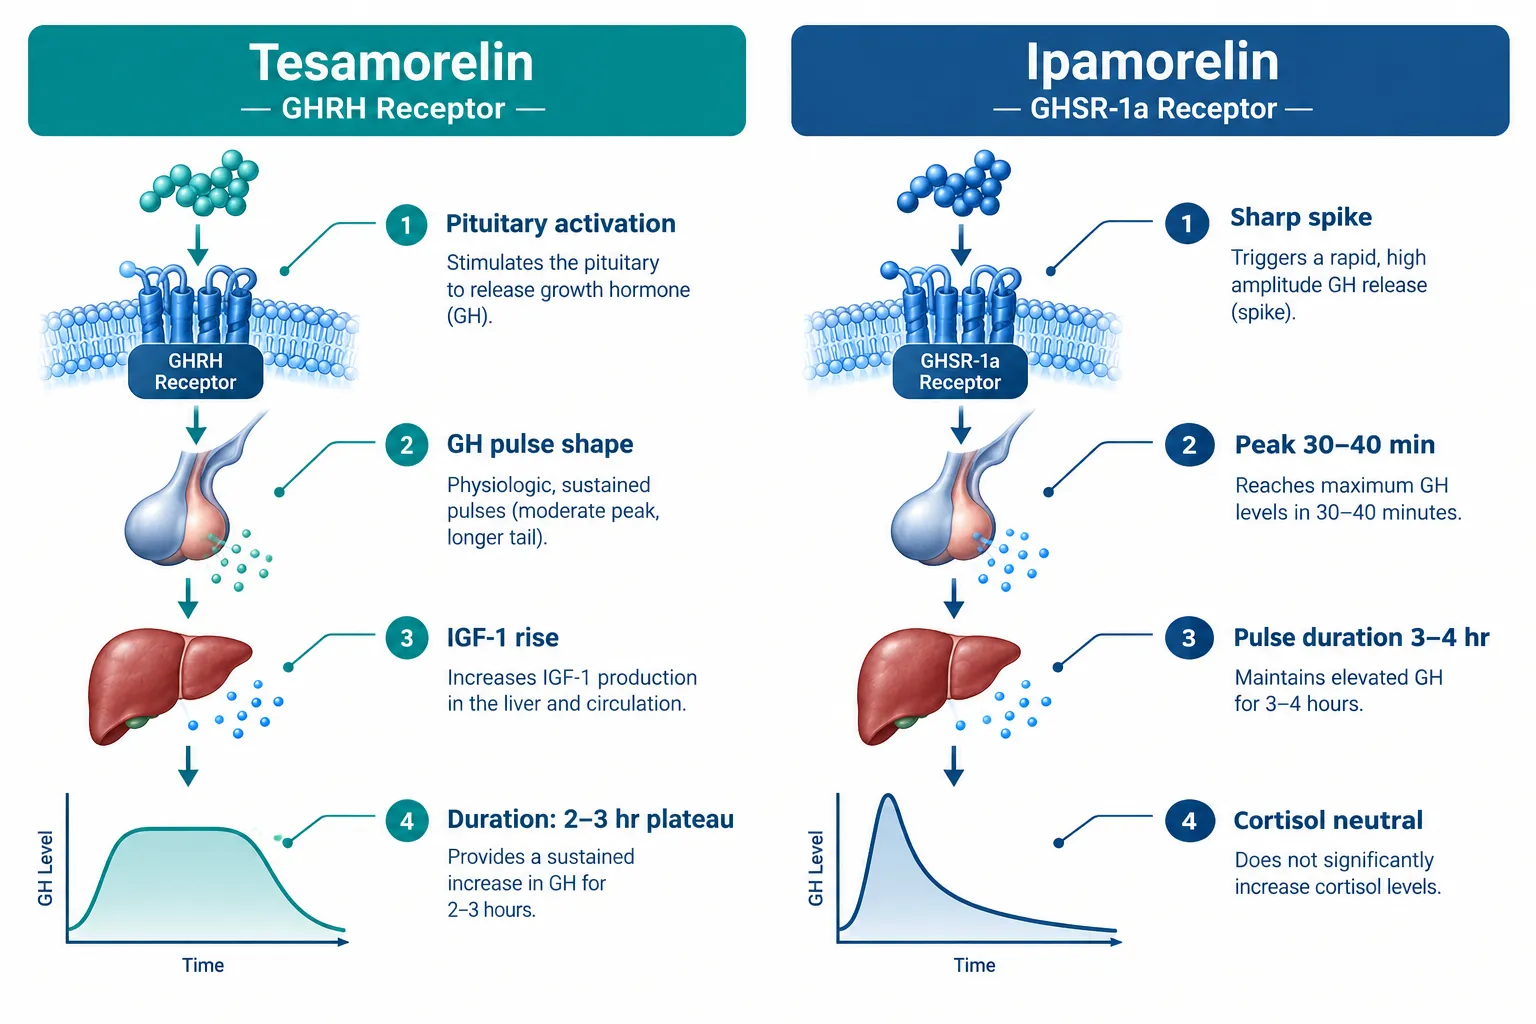
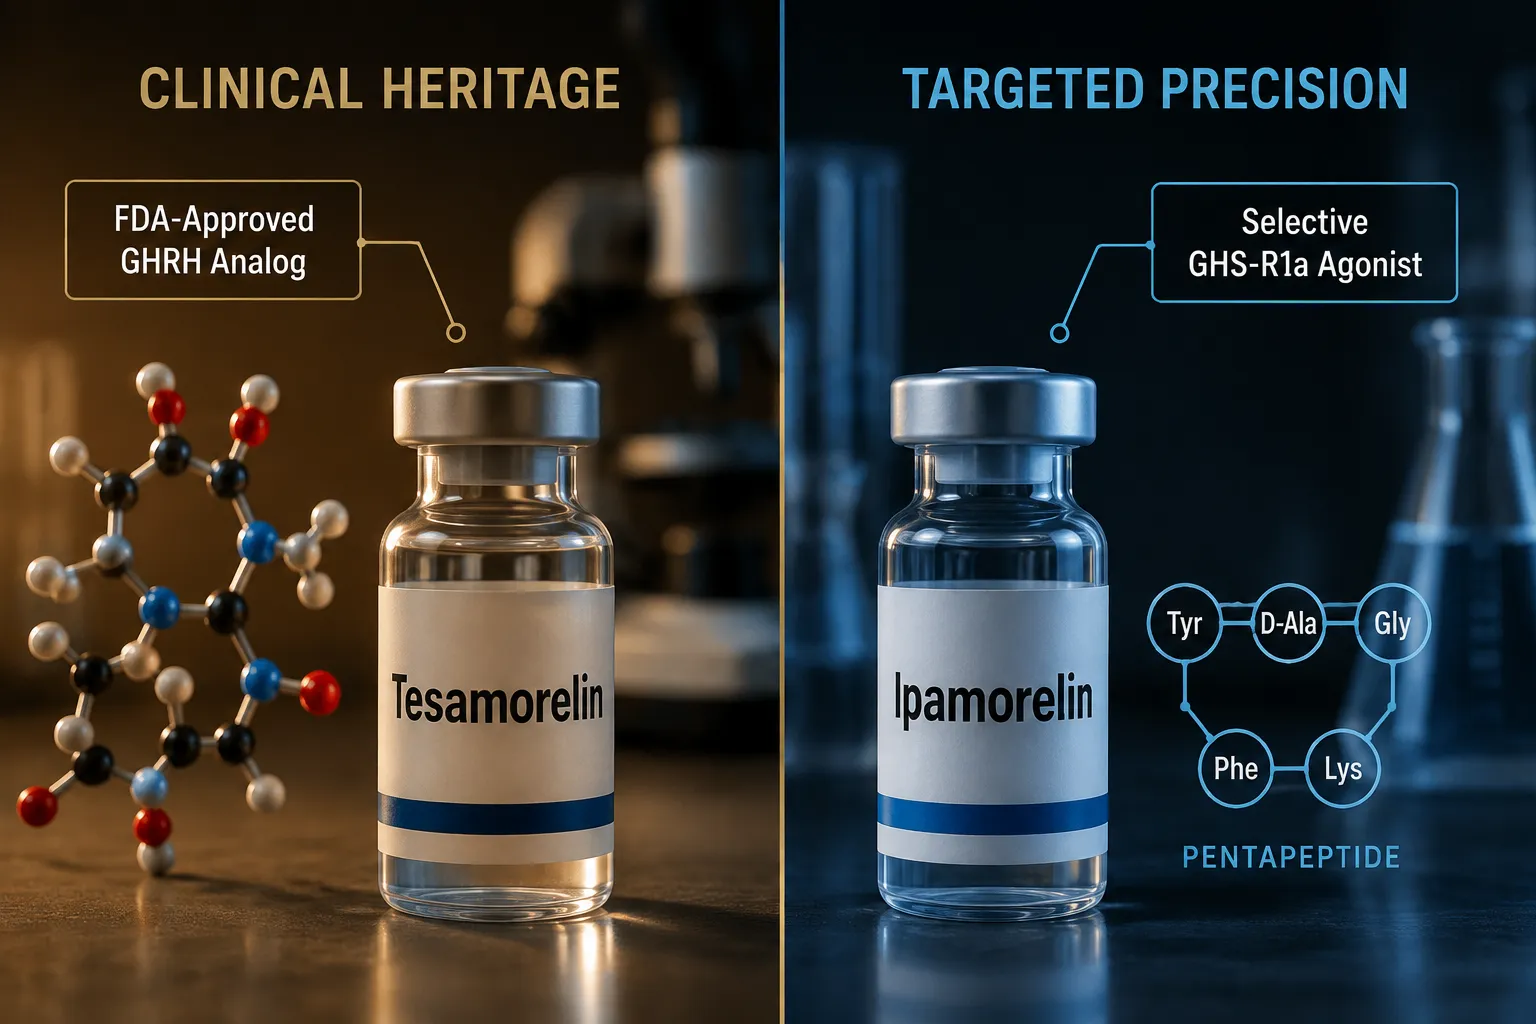
Tesamorelin, the FDA-approved GHRH analog marketed as EGRIFTA and EGRIFTA WR, has a median time to peak plasma concentration of about 0.15 hours and a mean elimination half-life of 26-38 minutes under repeated dosing. In healthy subjects, that half-life compresses to roughly 11 minutes. Updated prescribing data for the newer EGRIFTA WR formulation confirm that reformulation did not meaningfully extend signal duration, systemic exposure (Cmax and AUC) remained comparable to the original product. For those designing studies around this agent, the science behind tesa provides useful background on its receptor-level mechanism.
"A short plasma signal does not mean a short biological effect, it means the downstream cascade, including GH secretion and IGF-1 synthesis, must be measured on a timeline that respects the signal's architecture."
Receptor-Level Intent and the Ipamorelin Distinction
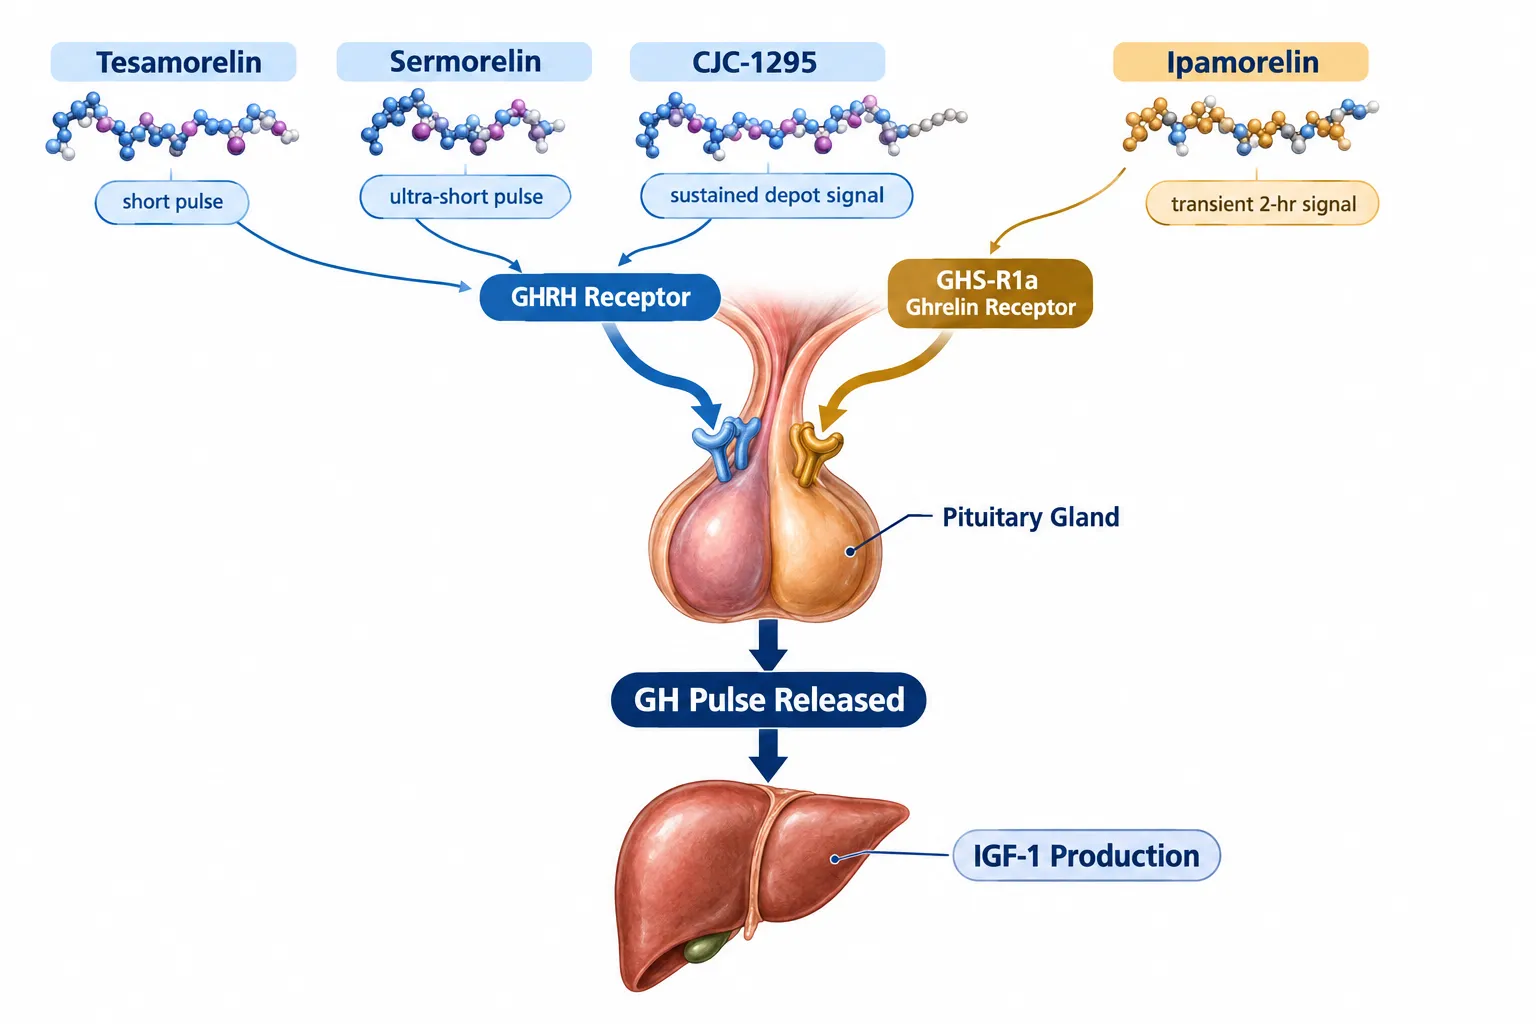
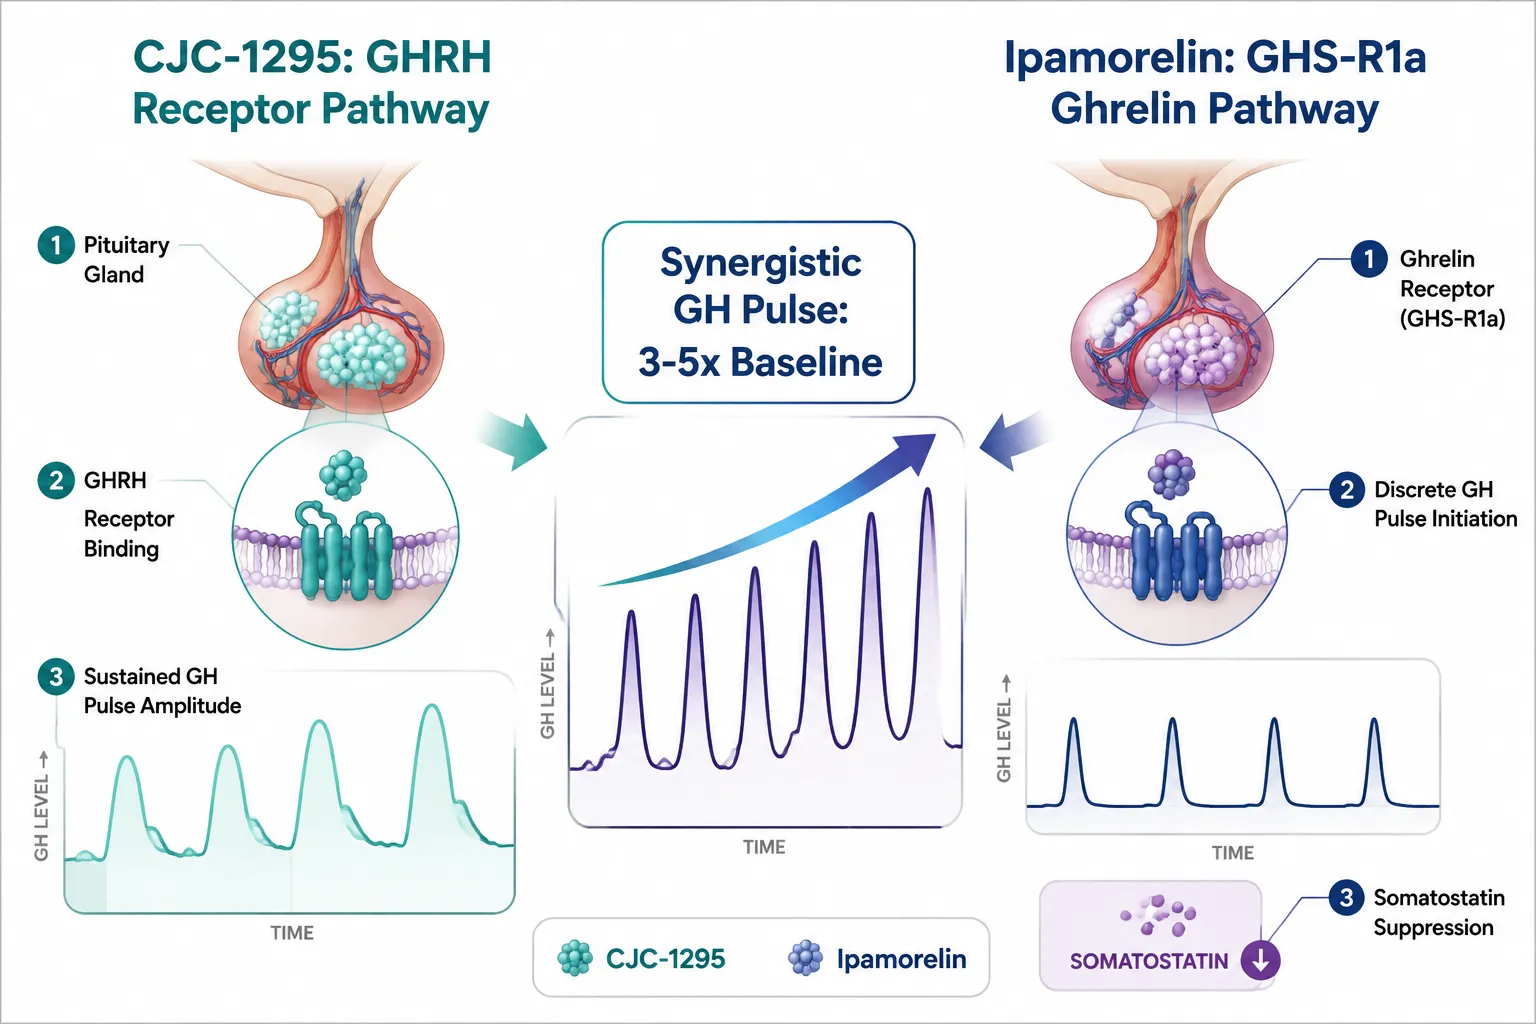
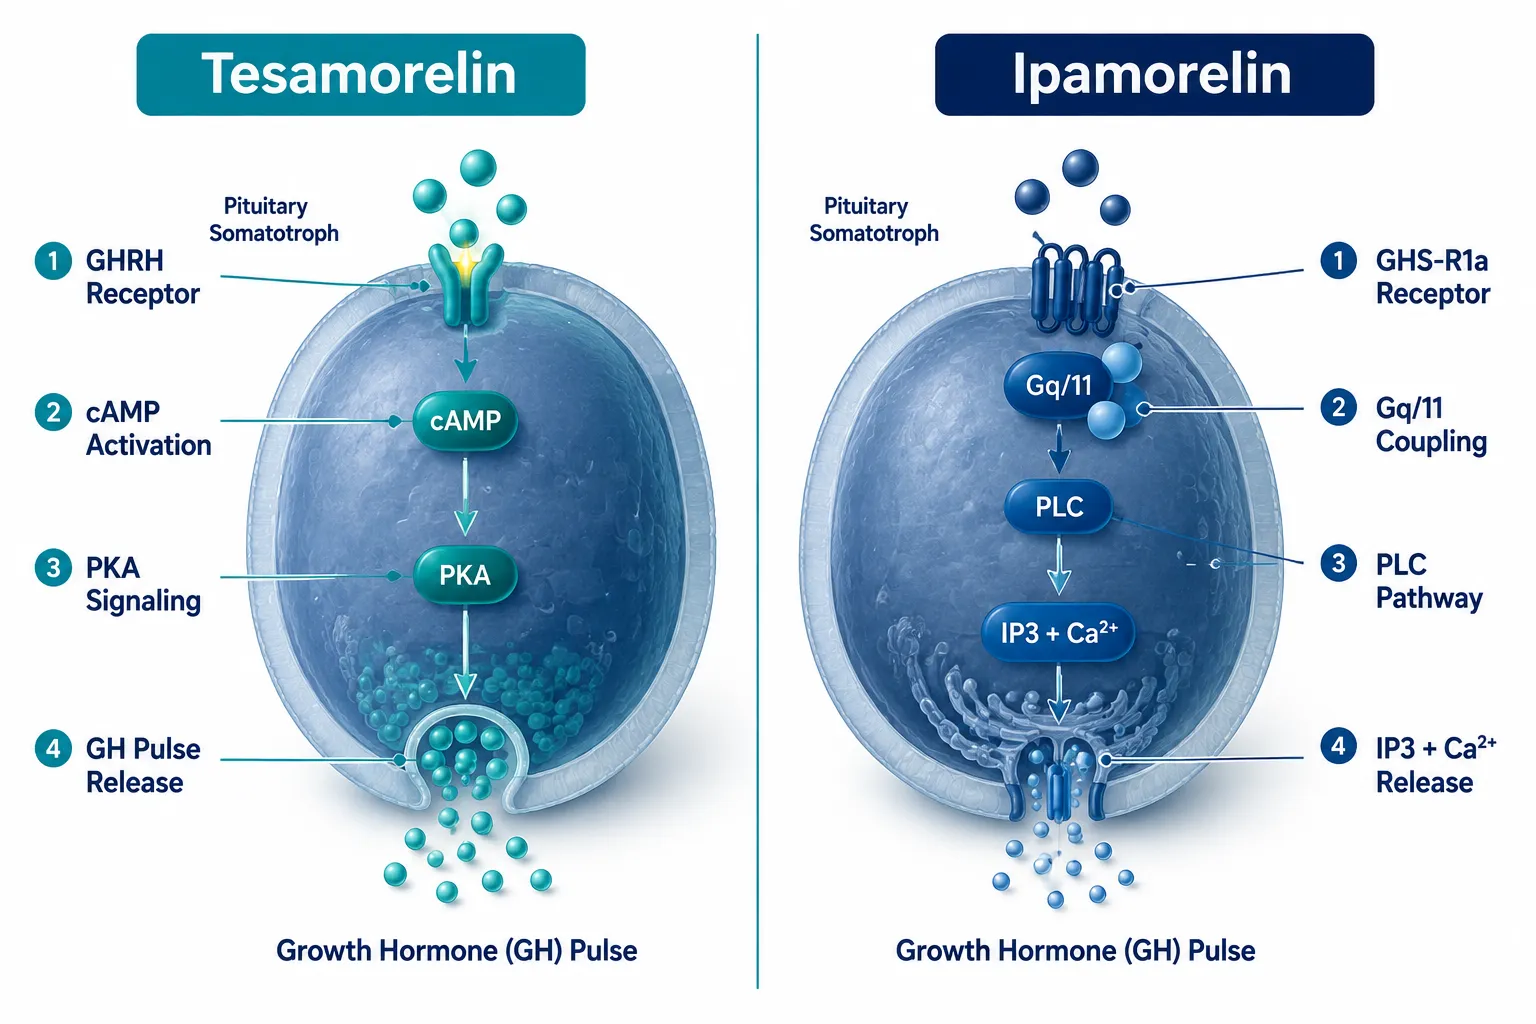
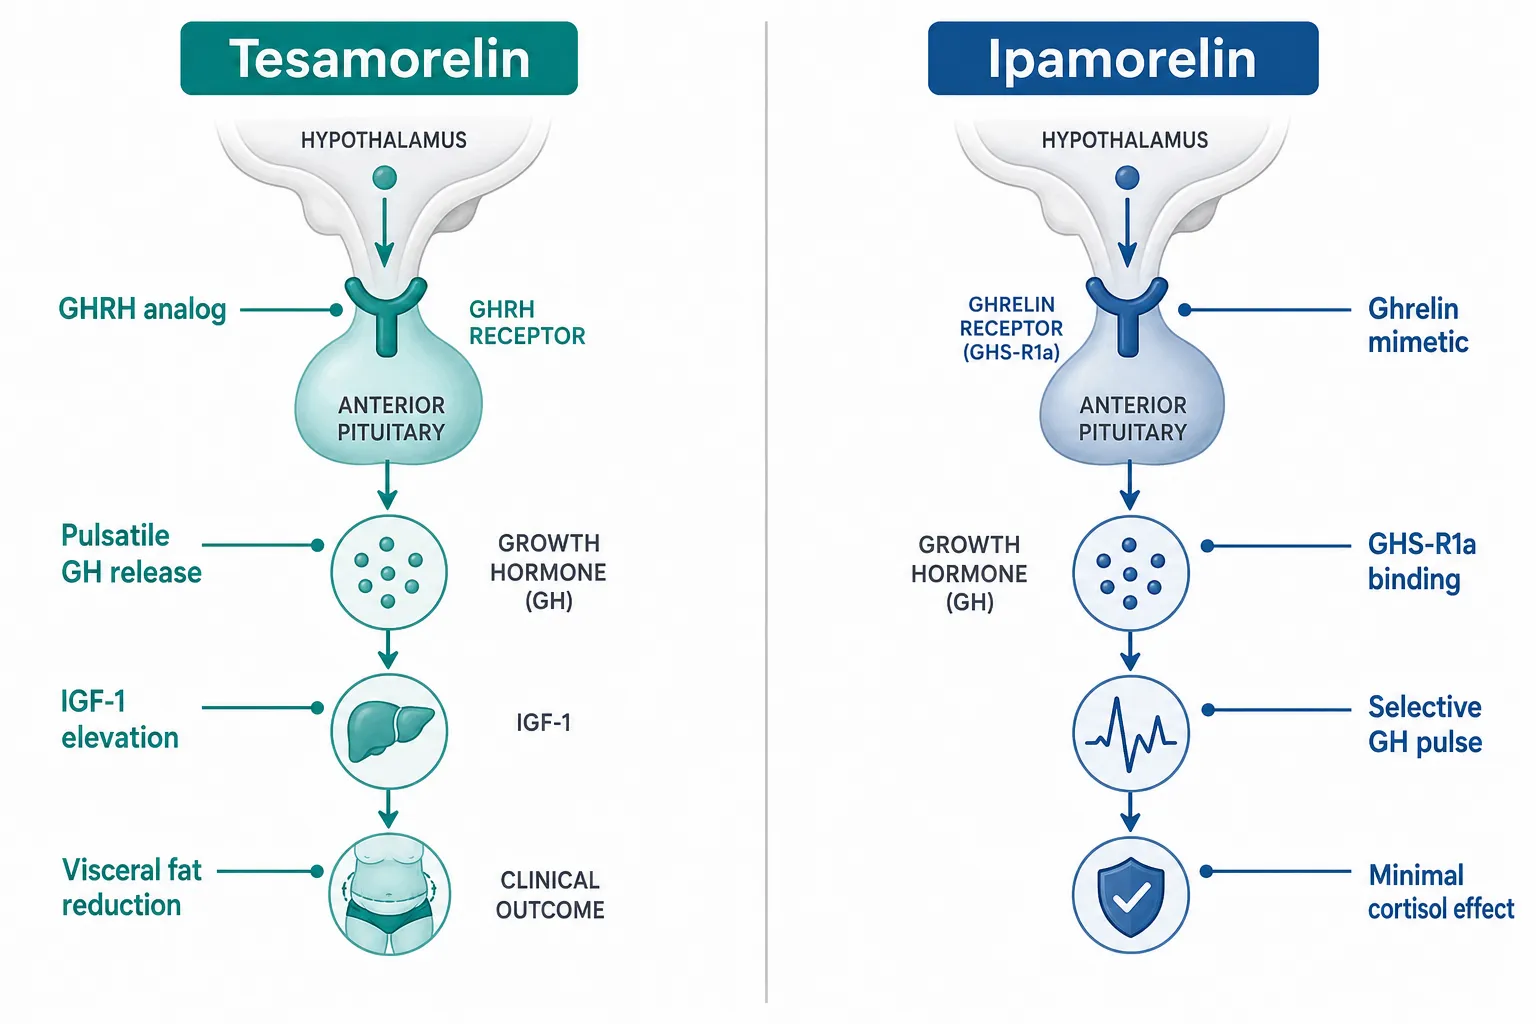
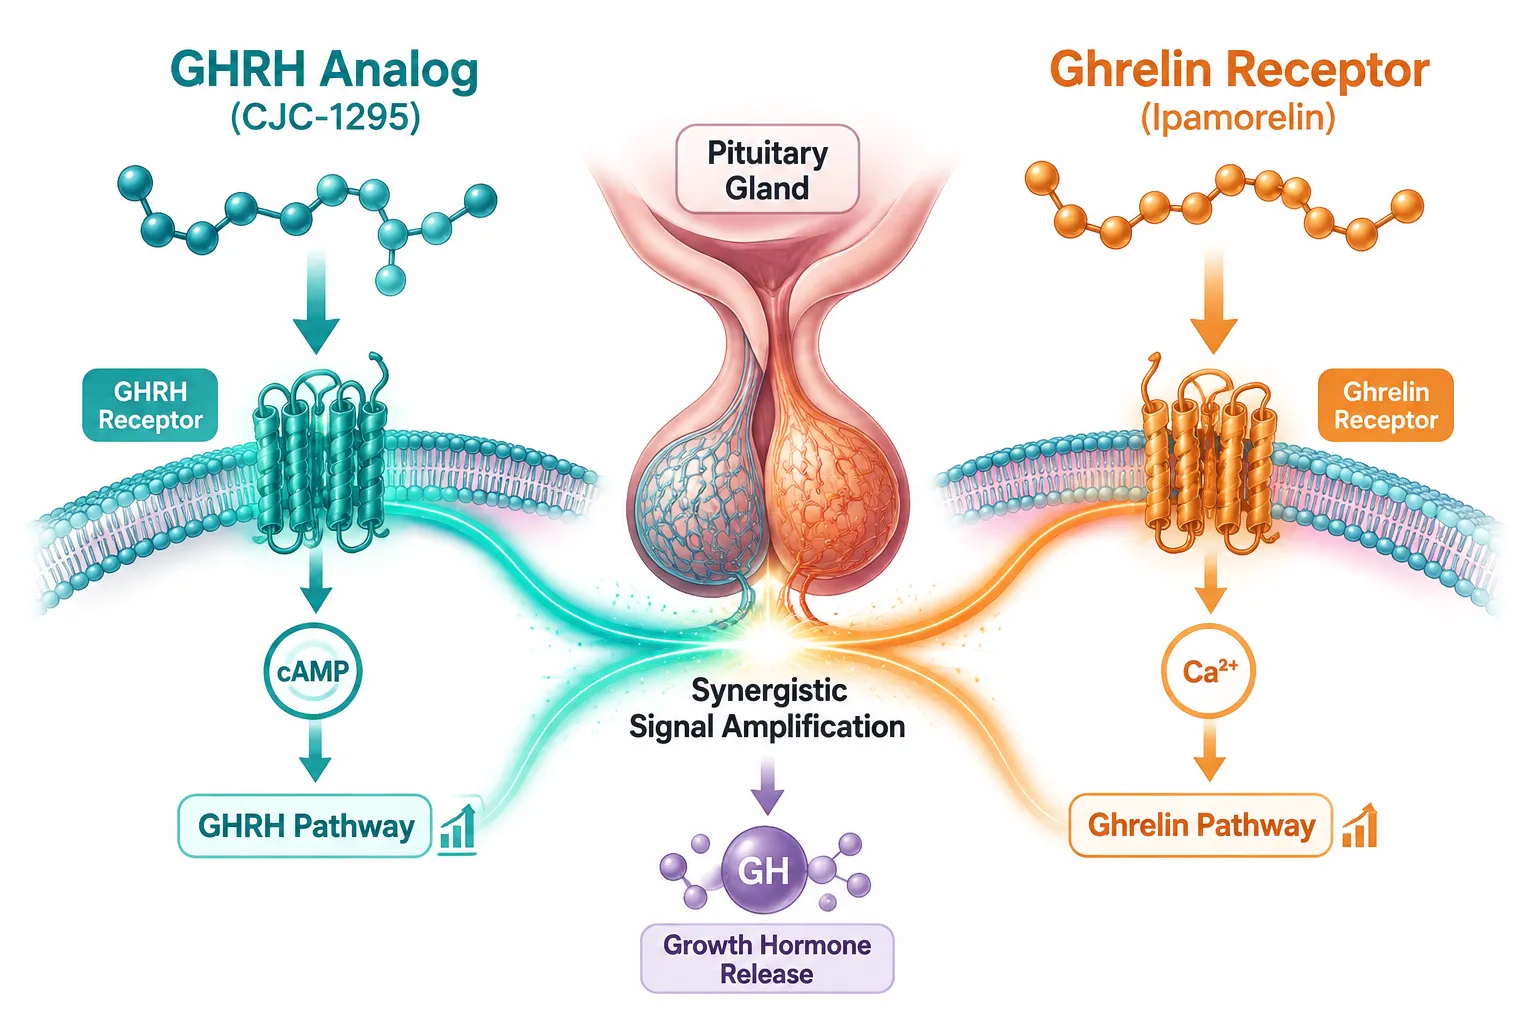
One of the most consequential design errors in secretagogue research is treating ipamorelin as interchangeable with GHRH analogs. It is not. Ipamorelin activates GHS-R1a, the ghrelin receptor, not the GHRH receptor. This receptor-level distinction has direct implications for combination protocols and signal-duration comparisons.
Ipamorelin's PK profile is notably cleaner than that of older GHRPs. Its terminal half-life sits around 2 hours, clearance is approximately 0.078 L/h/kg, and its volume of distribution at steady state is about 0.22 L/kg. The dose-proportional kinetics make it a tractable agent for controlled studies. Researchers interested in sourcing this compound for preclinical work can review options under buy ipamorelin online.
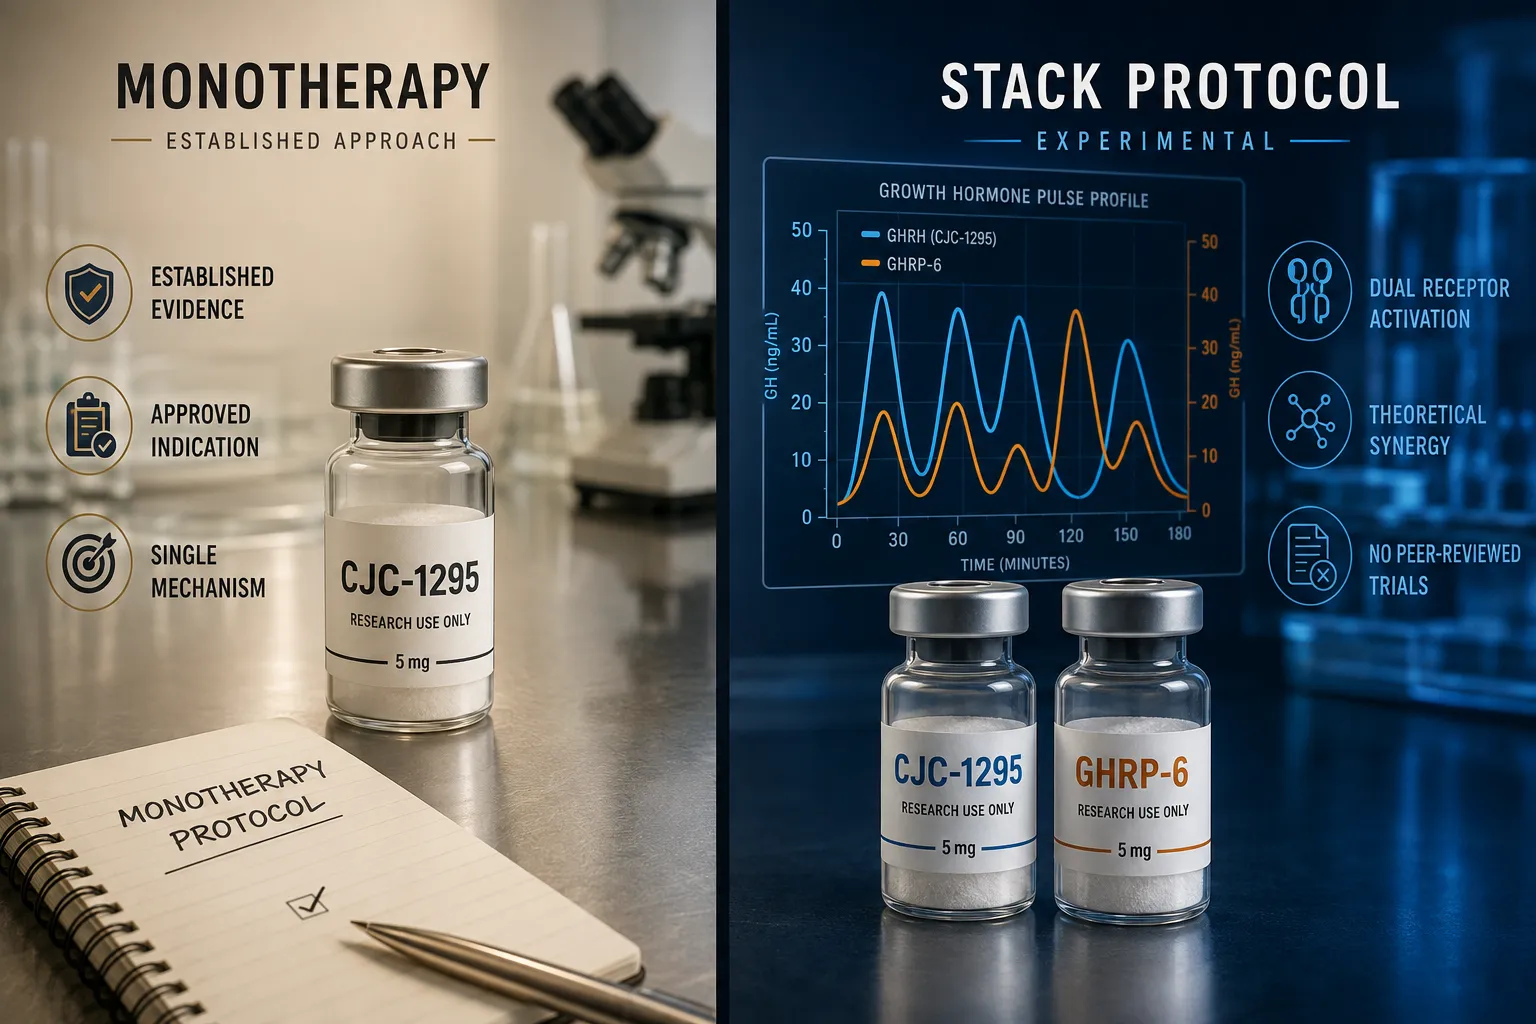
Because ipamorelin works through a separate receptor, combining it with a GHRH analog is theoretically additive, each agent hits a distinct node in the GH-release pathway. However, no completed human randomized controlled trial has tested the CJC-1295 plus ipamorelin stack. Signal-duration synergy claims for this combination are extrapolated from single-agent PK/PD data, not direct combination evidence. Any research protocol treating this combination as established is building on an incomplete evidentiary foundation.
For studies using multi-agent blends, the Sermorelin Ipamorelin CJC-1295 blend page outlines how these agents are commonly combined in research contexts, while the Tesamorelin AOD9604 CJC-1295 Ipamorelin 12mg blend illustrates multi-peptide formulation approaches.
DAC Status, Assay Timing, and IGF-1 Interpretation

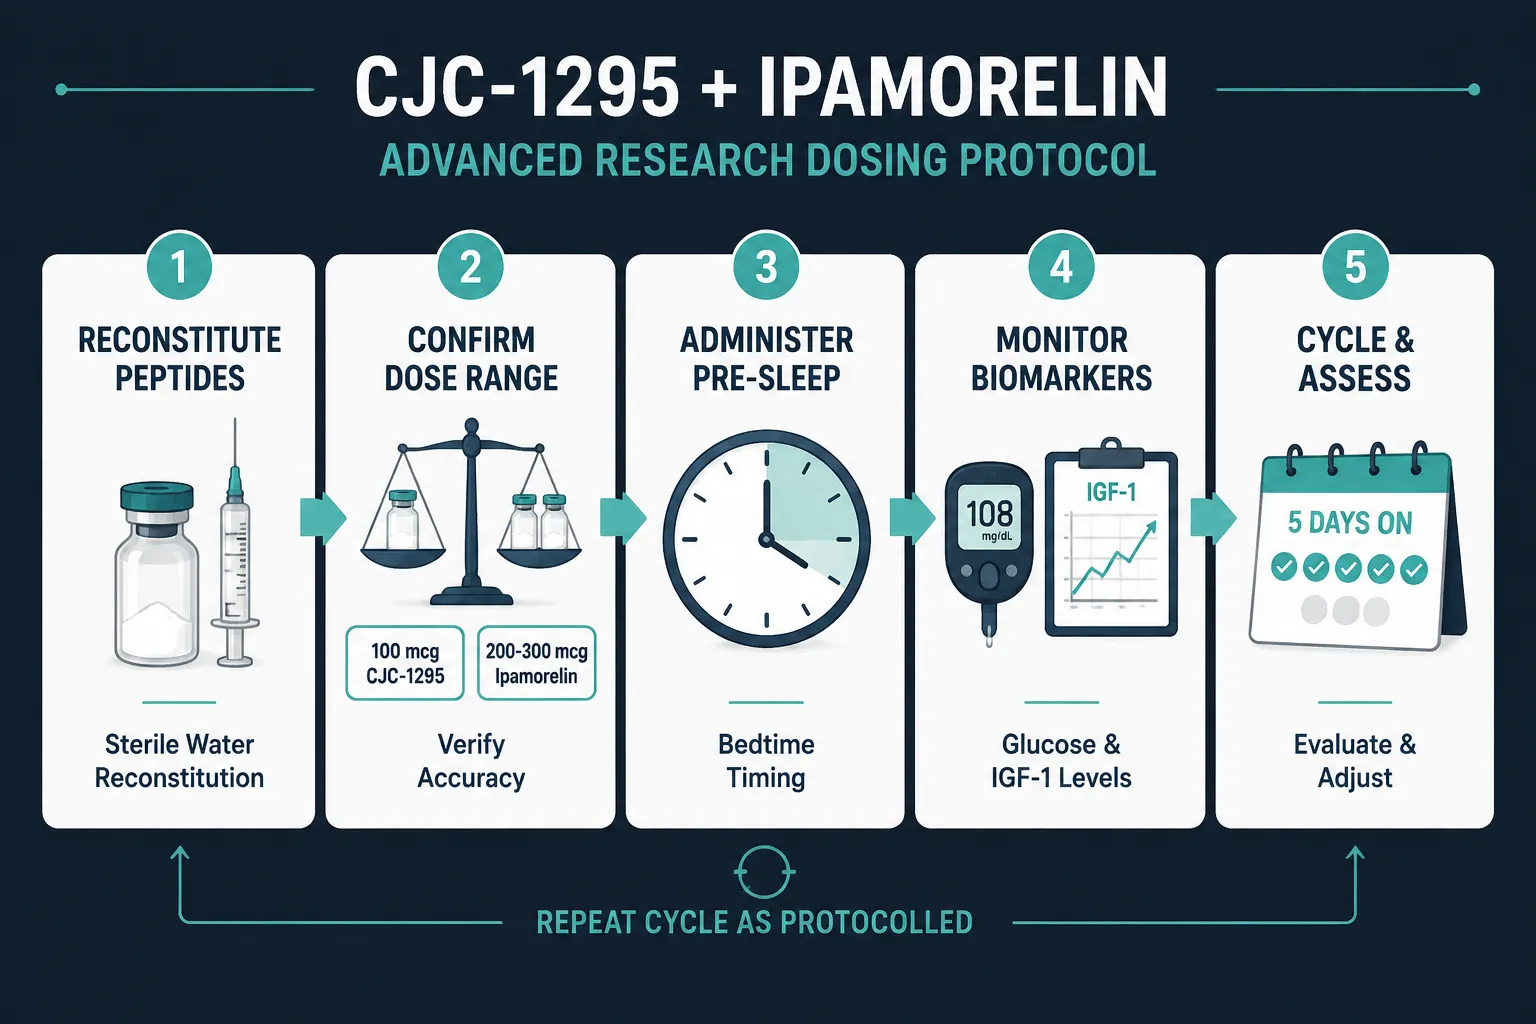
The DAC (Drug Affinity Complex) modification on CJC-1295 is not a minor formulation detail, it changes the fundamental experimental question. Without DAC, CJC-1295 behaves similarly to sermorelin: a short-acting GHRH analog cleared within minutes. With DAC, the half-life extends to 5.8-8.1 days, and a single subcutaneous injection produces GH elevations of roughly 2- to 10-fold for at least 6 days, with IGF-1 increases of approximately 1.5- to 3-fold persisting for 9-11 days.
This transforms the research design in three ways:
- Dosing frequency shifts from daily to weekly or biweekly.
- Assay timing must capture multi-day kinetics rather than a 30-60 minute post-dose window.
- IGF-1 as an endpoint becomes more meaningful because sustained GH elevation is required to drive meaningful IGF-1 synthesis; ultra-short agents like sermorelin or tesa generate IGF-1 changes through repeated daily pulses, not a single sustained signal.
For detailed pharmacokinetic comparisons of CJC-1295 with and without DAC, the dedicated CJC-1295 mechanism and pharmacokinetic comparison article is a primary reference.
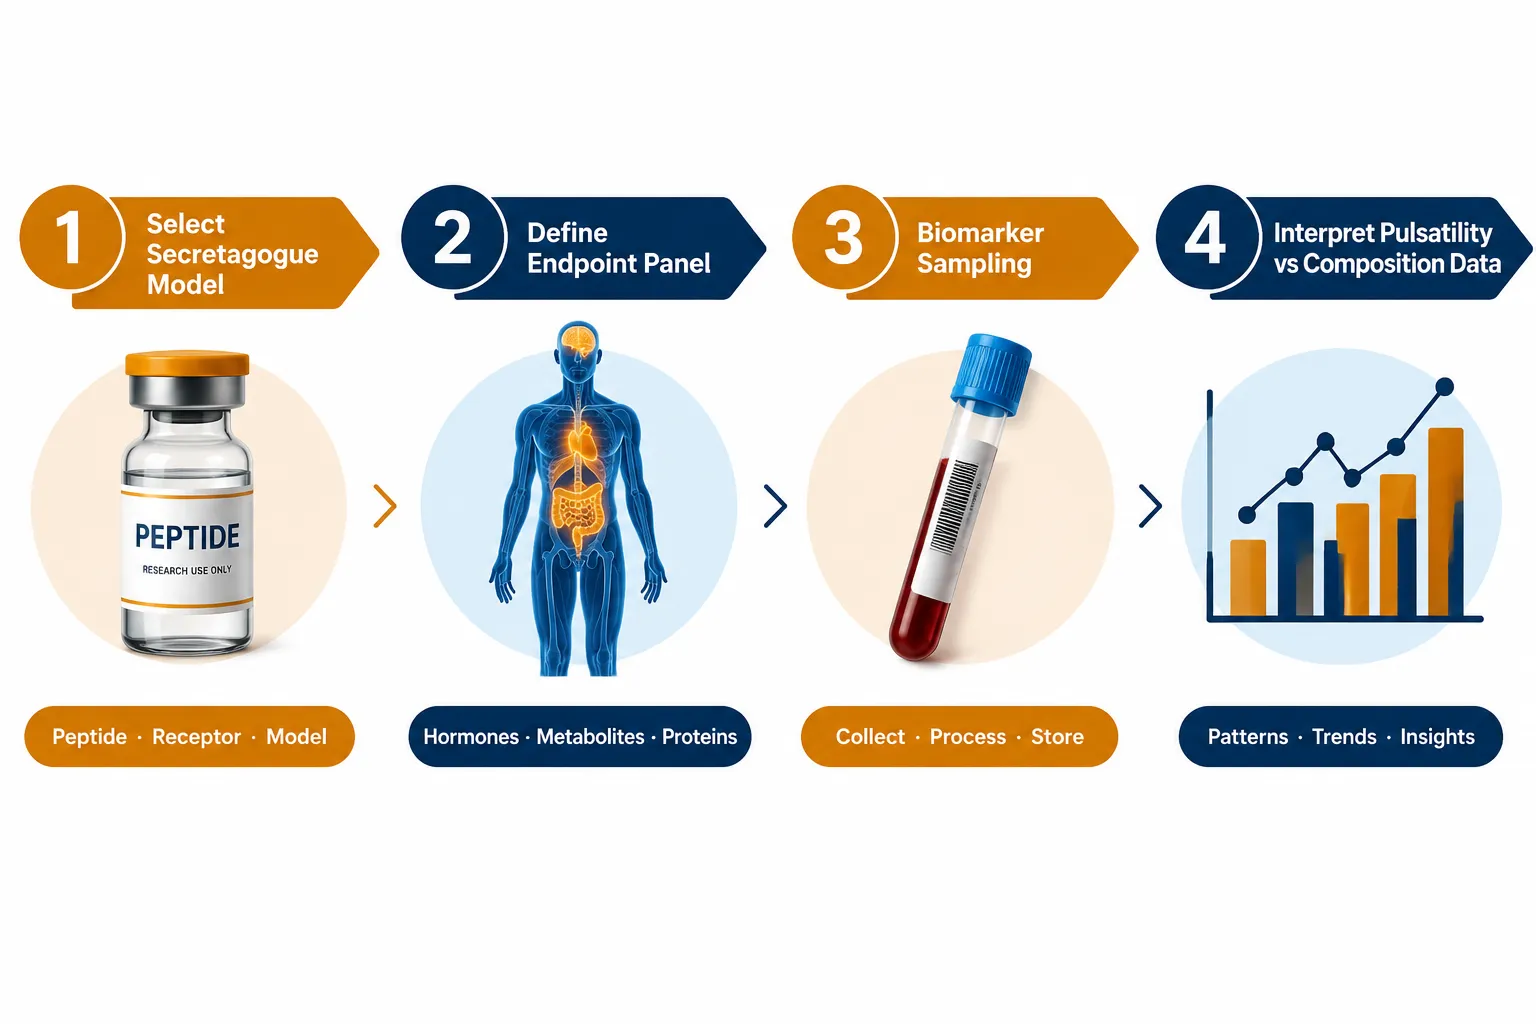
When designing assay protocols, the following timing framework applies:
- Sermorelin / Tesamorelin: Serum GH sampling at 15, 30, and 60 minutes post-dose; IGF-1 measured after at least 4 weeks of daily dosing.
- Ipamorelin: Serum GH sampling at 30, 60, and 120 minutes post-dose; IGF-1 measured after sustained multi-week exposure.
- CJC-1295 with DAC: Serum GH at 24, 48, and 96 hours post-dose; IGF-1 at days 7, 14, and 28 to capture accumulation across doses.
Misaligning assay windows with signal duration is one of the most common sources of false-negative results in secretagogue research. A study measuring GH at 4 hours post-tesa dose will miss the peak entirely.
Population PK/PD data from tesa trials in HIV-infected patients show approximately 34% higher systemic AUC compared with healthy subjects, despite similar Cmax and Tmax values. This exposure difference does not change the pulse-type time profile, it means downstream GH and IGF-1 responses may be amplified in certain populations, which must be accounted for in between-group comparisons. Researchers exploring tesa dosage parameters will find this population-level variability relevant to protocol calibration.
Conclusion
Growth-Hormone Secretagogue Research Design: Comparing Tesamorelin, CJC-1295, Ipamorelin, and Sermorelin by Signal Duration is ultimately a question of matching measurement strategy to mechanism. Each agent operates on a distinct timeline and at a distinct receptor, and treating them as interchangeable leads to flawed assay design and uninterpretable data.
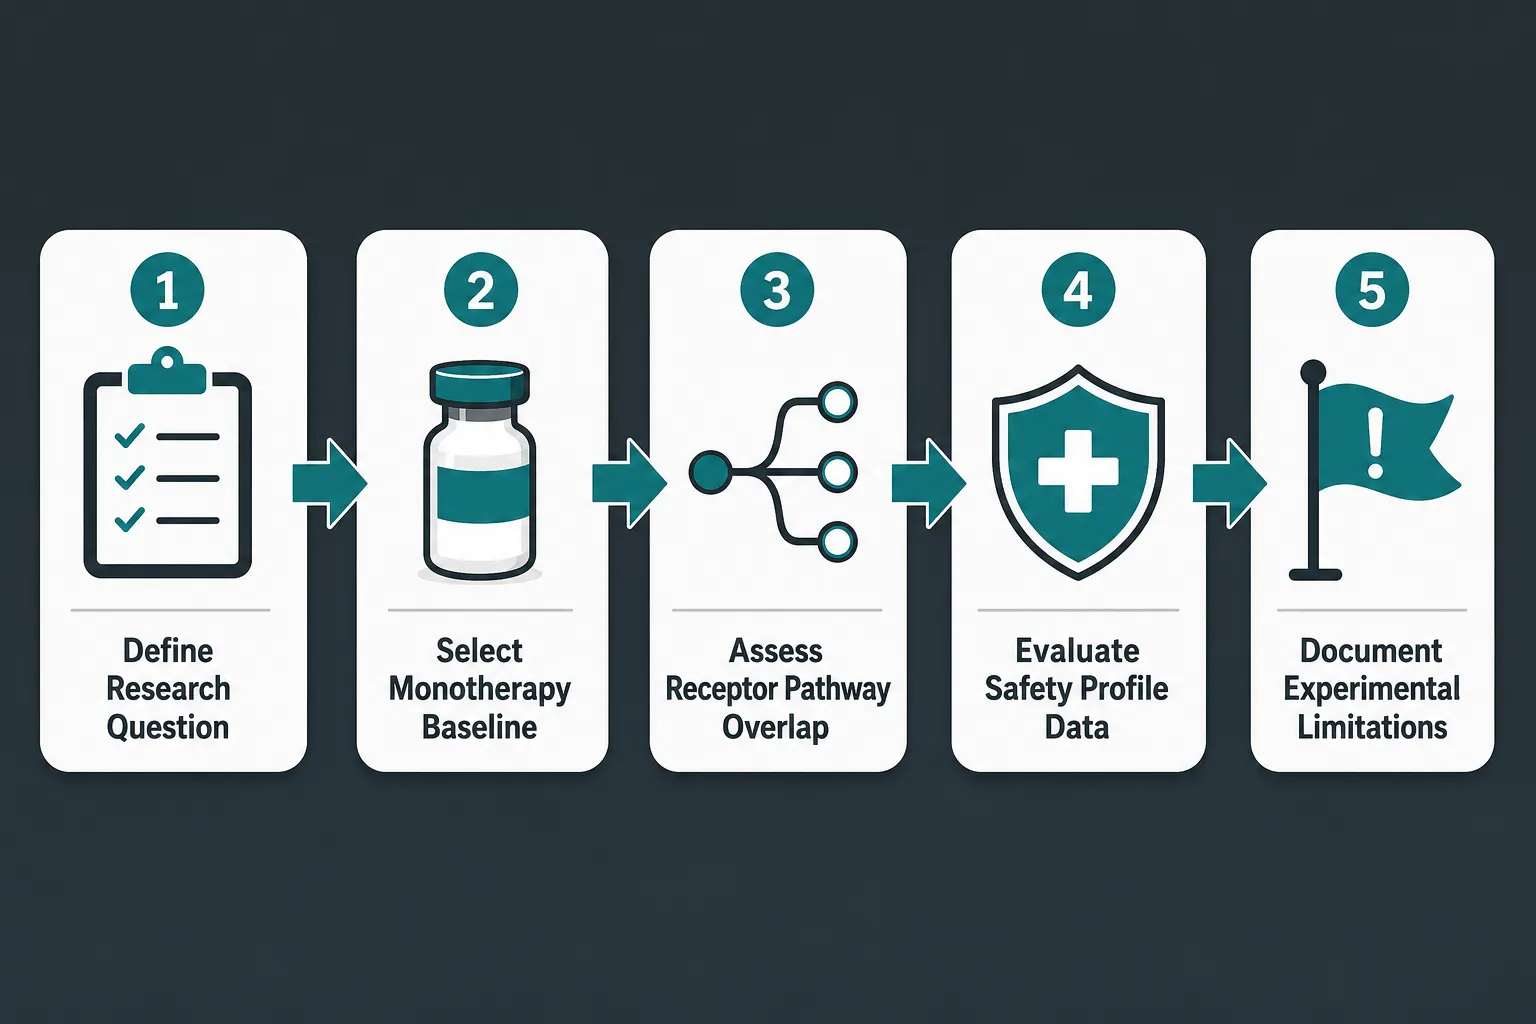
Actionable next steps for researchers in 2026:
- Classify agents by signal tier first, ultra-short (sermorelin, tesa), short (ipamorelin), or long-acting depot (CJC-1295 with DAC), before selecting endpoints or dosing intervals.
- Confirm DAC status on any CJC-1295 source before designing a protocol; the presence or absence of DAC changes the experimental question entirely.
- Align GH assay windows with each agent's Tmax and half-life; misaligned sampling is the most preventable source of false-negative results.
- Treat IGF-1 as a cumulative marker, not an acute one; interpret it only in the context of dosing duration and frequency appropriate to each agent's signal length.
- Avoid overstating combination evidence for CJC-1295 plus ipamorelin stacks until human randomized trial data are available.
Rigorous secretagogue research depends less on which peptide is chosen and more on whether the study design respects the biology of how each signal is generated, sustained, and cleared.