

Complement-Dependent Cytotoxicity in GLP-3 and BPC-157 Studies: What New Safety Data Signals Mean for Peptide Researchers in 2026
Fewer than ten serious adverse event reports in a public pharmacovigilance database might seem trivial, until those reports involve a peptide that millions of athletes and biohackers are already self-administering. As of September 2026, the FDA Adverse Event Reporting System lists ten serious reports linked to BPC-157 since 2021, a number that, combined with emerging immunogenicity concerns around GLP-3 receptor agonists, has pushed complement-dependent cytotoxicity (CDC) to the center of peptide safety discourse. Understanding what complement-dependent cytotoxicity in GLP-3 and BPC-157 studies means for peptide researchers in 2026 is no longer optional, it is a prerequisite for responsible laboratory work.
Key Takeaways
- Complement-dependent cytotoxicity is a specific immune mechanism in which antibody binding to a target cell activates the complement cascade, leading to cell lysis, and it is an underexamined endpoint in current peptide safety studies.
- BPC-157 has no FDA approval, is banned by WADA, and carries a Category 2 bulk substance designation; its human safety data remains limited to small pilots.
- GLP-3 receptor agonist research lacks published CDC-specific data as of 2026, requiring researchers to extrapolate from broader peptide immunology frameworks.
- Ten serious FAERS reports involving BPC-157 since 2021 represent an early pharmacovigilance signal that warrants structured monitoring protocols.
- Practical CDC risk assessment for peptide labs should incorporate purity verification, anti-drug antibody screening, and systematic adverse event cross-referencing.
Understanding Complement-Dependent Cytotoxicity in the Context of Peptide Research
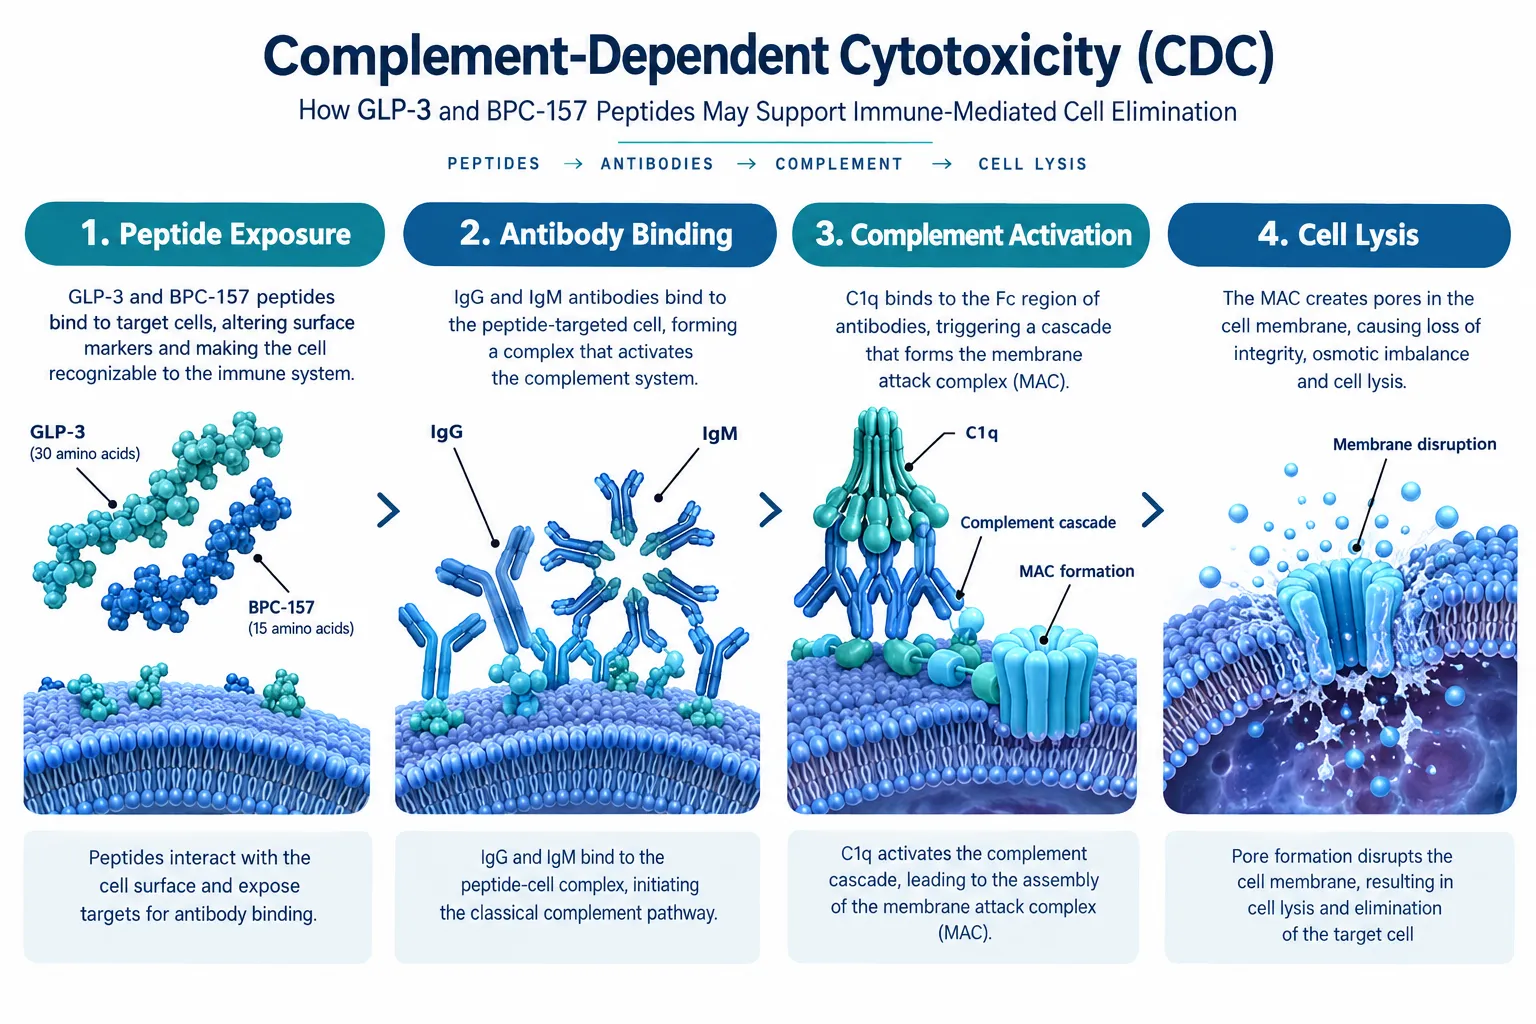
Complement-dependent cytotoxicity describes a process in which an antibody binds to an antigen on a cell surface, recruits the C1q complement protein, and triggers a cascade that ultimately forms the membrane attack complex (MAC). The MAC punches holes in the target cell membrane, causing lysis. In oncology, this mechanism is deliberately exploited by therapeutic monoclonal antibodies. In peptide research, however, it represents an unintended and largely unmonitored risk.
Why does this matter for small synthetic peptides? Historically, low-molecular-weight peptides were considered poorly immunogenic. More recent immunology literature has complicated that assumption. Peptide aggregation, carrier protein conjugation, impurities from synthesis, and route of administration can all elevate immunogenic potential. When a peptide triggers an antibody response, those antibodies can theoretically engage complement, particularly if the peptide localizes to cell surfaces or forms immune complexes.
For researchers working with GLP-3 peptide products or reviewing GLP-3R 30mg peptide formulations, this is directly relevant. GLP-3 receptor agonists are structurally related to incretin-class peptides, a class that has demonstrated measurable immunogenicity in clinical settings. No peer-reviewed CDC-specific data for GLP-3 analogs has entered the public domain as of mid-2026, but the structural and mechanistic parallels with GLP-1 and dual agonist compounds make CDC screening a logical precaution.
"The absence of published complement data is not evidence of complement safety, it is a gap that 2026 research protocols should be designed to close."
Key factors that elevate CDC risk in synthetic peptides include:
- Aggregation propensity at physiological pH and temperature
- Synthesis impurities that act as hapten carriers
- Repeat dosing schedules that allow antibody titers to build
- Intravenous or subcutaneous routes that maximize systemic exposure
BPC-157 Safety Signals: What the 2025-2026 Data Actually Shows

BPC-157 (Body Protection Compound-157) is a synthetic pentadecapeptide derived from a gastric protein sequence. Its preclinical profile is genuinely striking: no organ toxicity has been identified in animal models, and no lethal dose was established even at 2 g/kg. A small intravenous safety pilot published in 2025, involving two subjects receiving 10-20 mg, reported no acute toxicity. These data points have been widely cited in the peptide community as evidence that BPC-157 is "safe and well-tolerated."
That framing deserves scrutiny. Two subjects do not constitute a safety dataset in any statistically meaningful sense. Aggregate human data as of early 2026 consists of small pilots and limited trials with no systematic immune or complement safety endpoints. Critical analysis published in 2026 has specifically challenged the leap from "no acute toxicity in a two-person pilot" to broad safety claims.
Regulatory and sports-medicine context in 2026:
| Parameter | Status |
|---|---|
| FDA Approval | Not approved |
| WADA Classification | Banned substance |
| Bulk Substance Category | Category 2 |
| FAERS Serious Reports (since 2021) | 10 reports |
| Immunogenicity Assessment | Formal regulatory concern |
The ten serious FAERS reports are a pharmacovigilance signal, not a confirmed causal link. However, regulatory guidance issued in July 2026 explicitly lists immunogenicity and impurity concerns as primary reasons for BPC-157's Category 2 bulk substance designation. The angiogenic properties of BPC-157, one of its most studied efficacy mechanisms, also raise long-term questions, since uncontrolled angiogenesis could theoretically interact with complement-mediated inflammatory pathways.
Researchers sourcing BPC-157 for preclinical work should prioritize purity documentation. This connects directly to CDC risk: synthesis impurities are a known driver of unwanted immunogenicity. Platforms that provide wound healing peptide research materials with verified purity certificates reduce one of the most controllable CDC risk variables.
For comparison, researchers familiar with mitochondria-targeted peptides like SS-31 can review SS-31 10mg research peptide considerations to understand how purity and formulation standards are applied to a structurally distinct but similarly small synthetic peptide.
A Practical CDC Risk-Assessment Framework for Peptide Labs in 2026
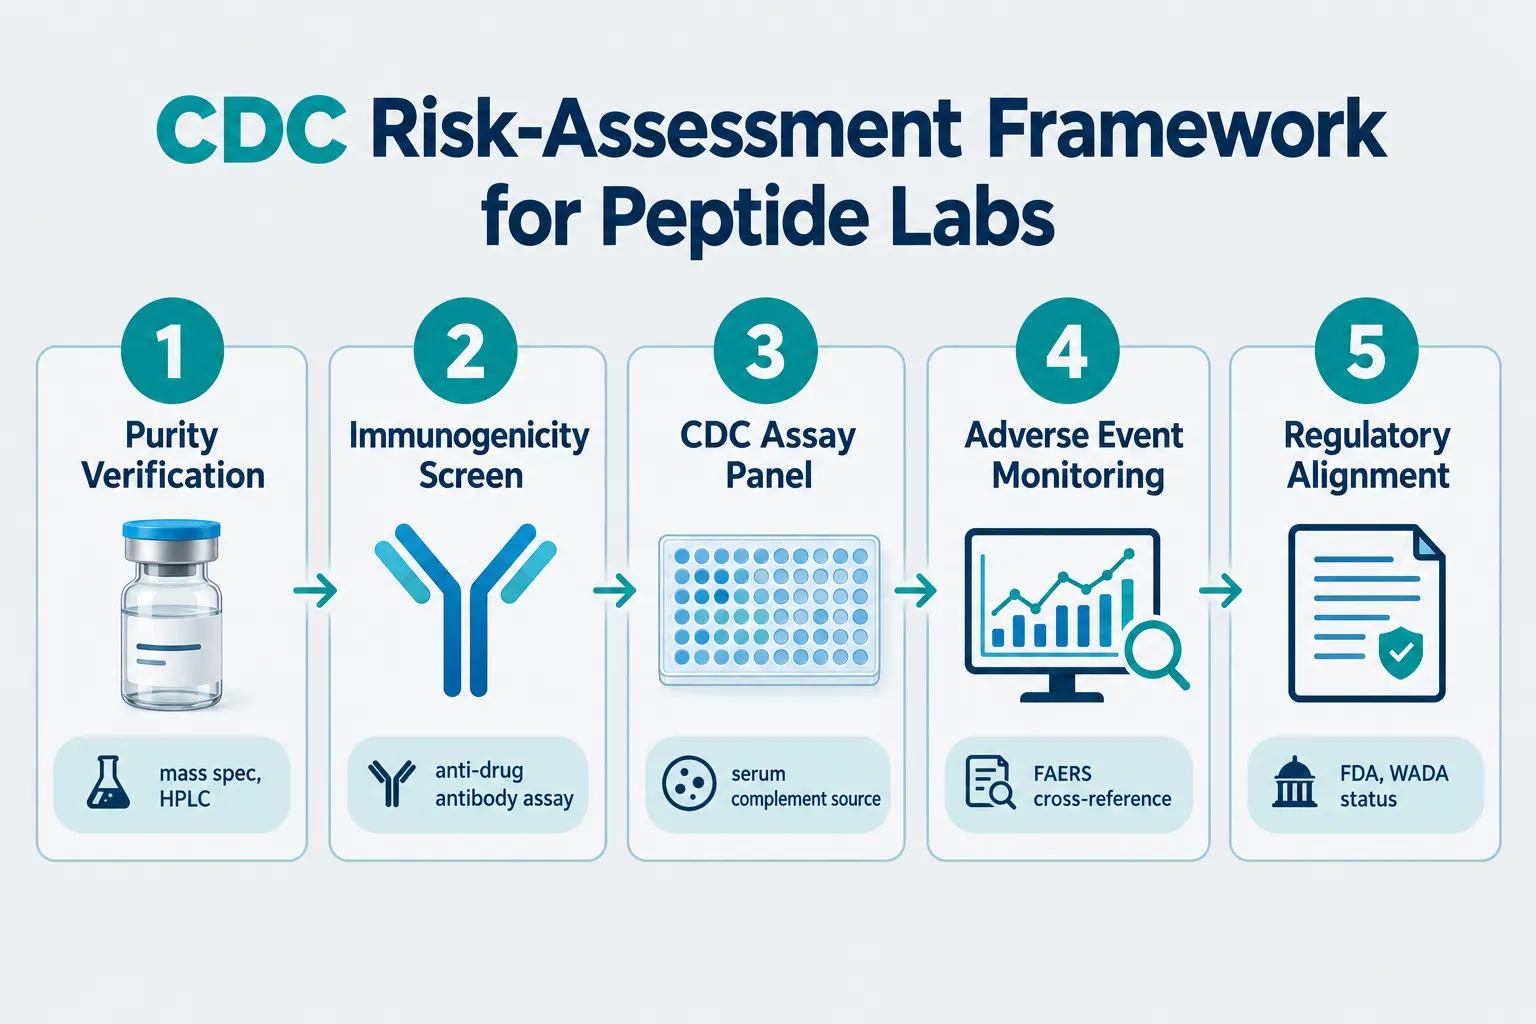
Given the data gaps outlined above, what should a peptide research laboratory actually do in 2026? The following framework synthesizes current immunology best practices with the specific signals emerging from BPC-157 and GLP-3 research.
Step 1: Verify Peptide Purity Before Any Biological Assay
Mass spectrometry and HPLC purity confirmation should be non-negotiable. Impurities above 1% are a meaningful immunogenicity risk factor. Researchers exploring GLP-3R 10mg peptide formulations should request certificates of analysis that specify both purity percentage and identified impurity profiles.
Step 2: Conduct Anti-Drug Antibody (ADA) Screening
ADA assays detect whether a peptide is generating an antibody response in the test system. Positive ADA results should trigger CDC-specific follow-up assays using complement-active human serum.
Step 3: Run a Formal CDC Assay Panel
Standard CDC assays use target cells incubated with the peptide-antibody complex plus complement source. Cell viability readouts (e.g., calcein-AM or LDH release) quantify lytic activity. This step is standard in biologic drug development but is largely absent from current peptide research protocols.
Step 4: Cross-Reference Adverse Event Databases
FAERS cross-referencing should be part of any ongoing safety monitoring plan. The ten BPC-157 serious reports represent a baseline; researchers should track whether this number changes as 2026 progresses.
Step 5: Align with Current Regulatory Guidance
Researchers should document FDA and WADA status for every compound in active study. For peptides with known regulatory concerns, institutional review processes should include explicit immunogenicity risk sections.
Researchers interested in related peptide safety comparisons may find value in reviewing Tesamorelin peptide benefits as a case study of an FDA-approved peptide with a documented safety and immunogenicity profile, a useful contrast to the uncharted territory of BPC-157 and GLP-3.
Conclusion
Complement-dependent cytotoxicity in GLP-3 and BPC-157 studies represents one of the most consequential underexamined safety endpoints in peptide research as of 2026. The data landscape is characterized by preclinical promise, minimal human evidence, and a growing pharmacovigilance signal that demands structured attention. The practical path forward is clear: implement purity verification, add ADA and CDC assays to standard safety panels, monitor FAERS actively, and treat regulatory designations as meaningful risk signals rather than bureaucratic obstacles.
Actionable next steps for peptide researchers:
- Audit current protocols for the presence or absence of CDC-specific endpoints
- Require HPLC and mass spec purity data for every peptide batch used in biological assays
- Establish a baseline ADA screening step before any repeat-dose in vitro or in vivo work
- Document WADA and FDA status for all compounds in active research files
- Review emerging 2026-2027 literature on incretin-class peptide immunogenicity as a predictive framework for GLP-3 analog safety
The field is moving quickly. Labs that build CDC risk assessment into their standard operating procedures now will be better positioned as regulatory scrutiny of research peptides intensifies through 2027.


Leave a Reply
Want to join the discussion?Feel free to contribute!