Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: blood pressure reduction

Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together

Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together

October 8, 2026/0 Comments/in Uncategorized/by

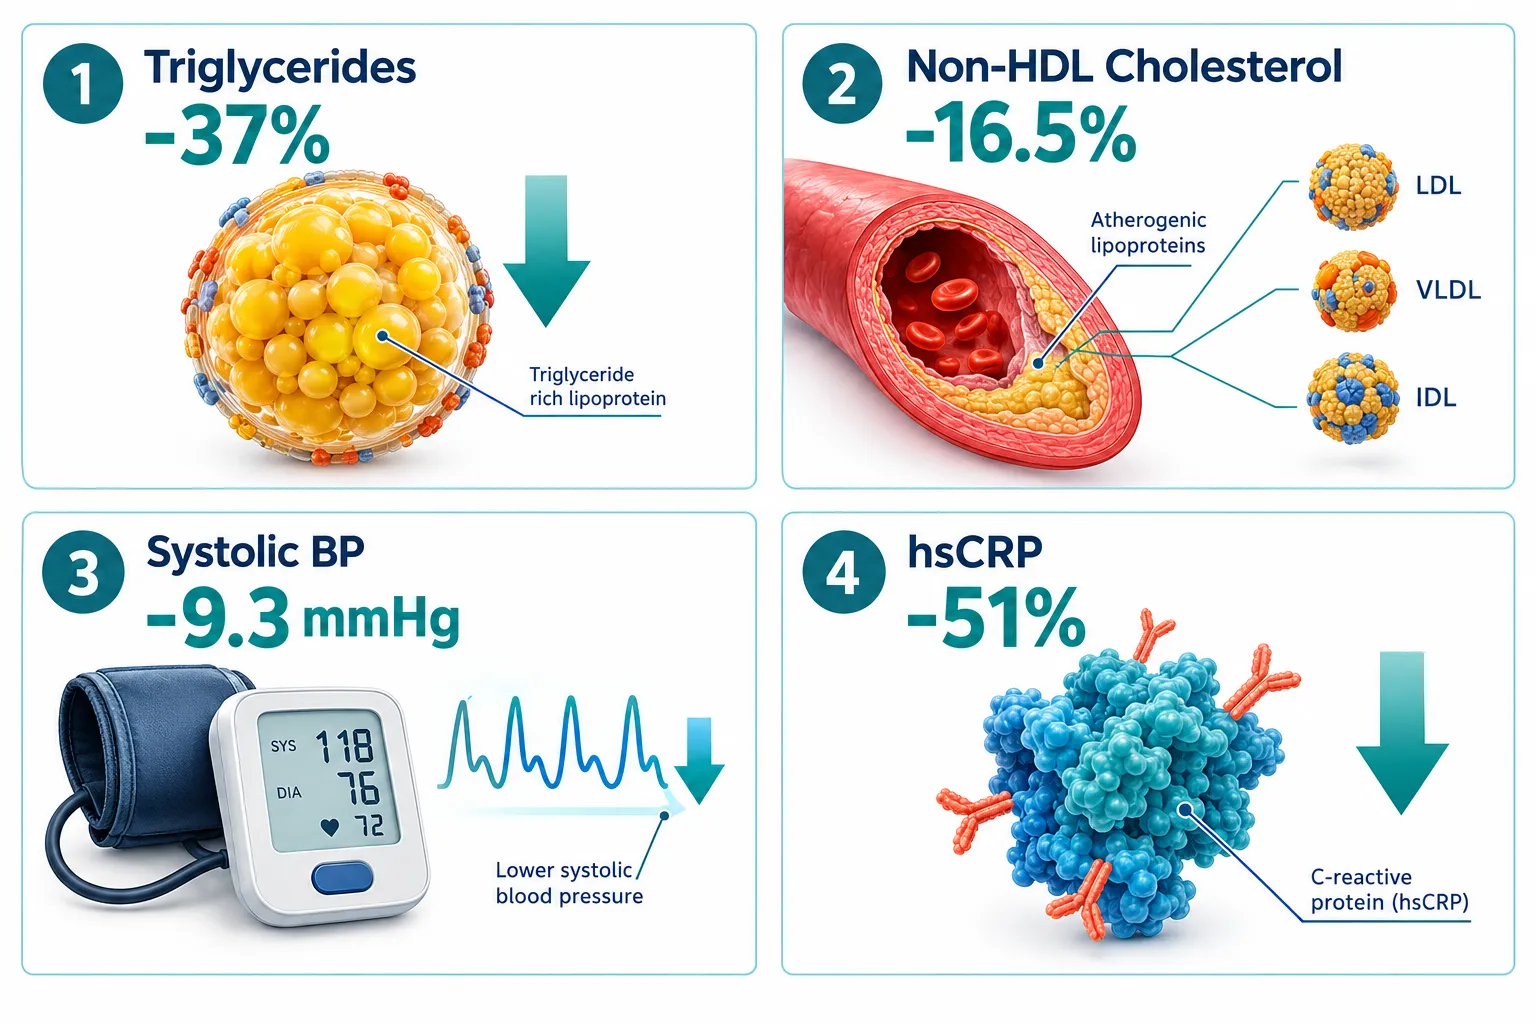
A 51% drop in high-sensitivity C-reactive protein alongside a 37% reduction in triglycerides, recorded in the same patients, at the same 80-week timepoint, is not a coincidence. It is a signal that demands careful interpretation. The TRIUMPH phase 3 program has now generated a dense cardiometabolic dataset around retatrutide, and understanding how to read Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together requires separating what the numbers show from what they can, and cannot, prove about cardiovascular outcomes.

Key Takeaways

  • Retatrutide 12 mg produced mean weight loss of 22.6% in TRIUMPH-3, alongside reductions of 37% in triglycerides, 16.5% in non-HDL cholesterol, 9.3 mmHg in systolic blood pressure, and 51.2% in hsCRP at 80 weeks.
  • Across broader obesity populations in TRIUMPH-1 and TRIUMPH-4, these cardiometabolic effects were even larger, reaching 39.5% triglyceride reduction and 58.3% hsCRP reduction.
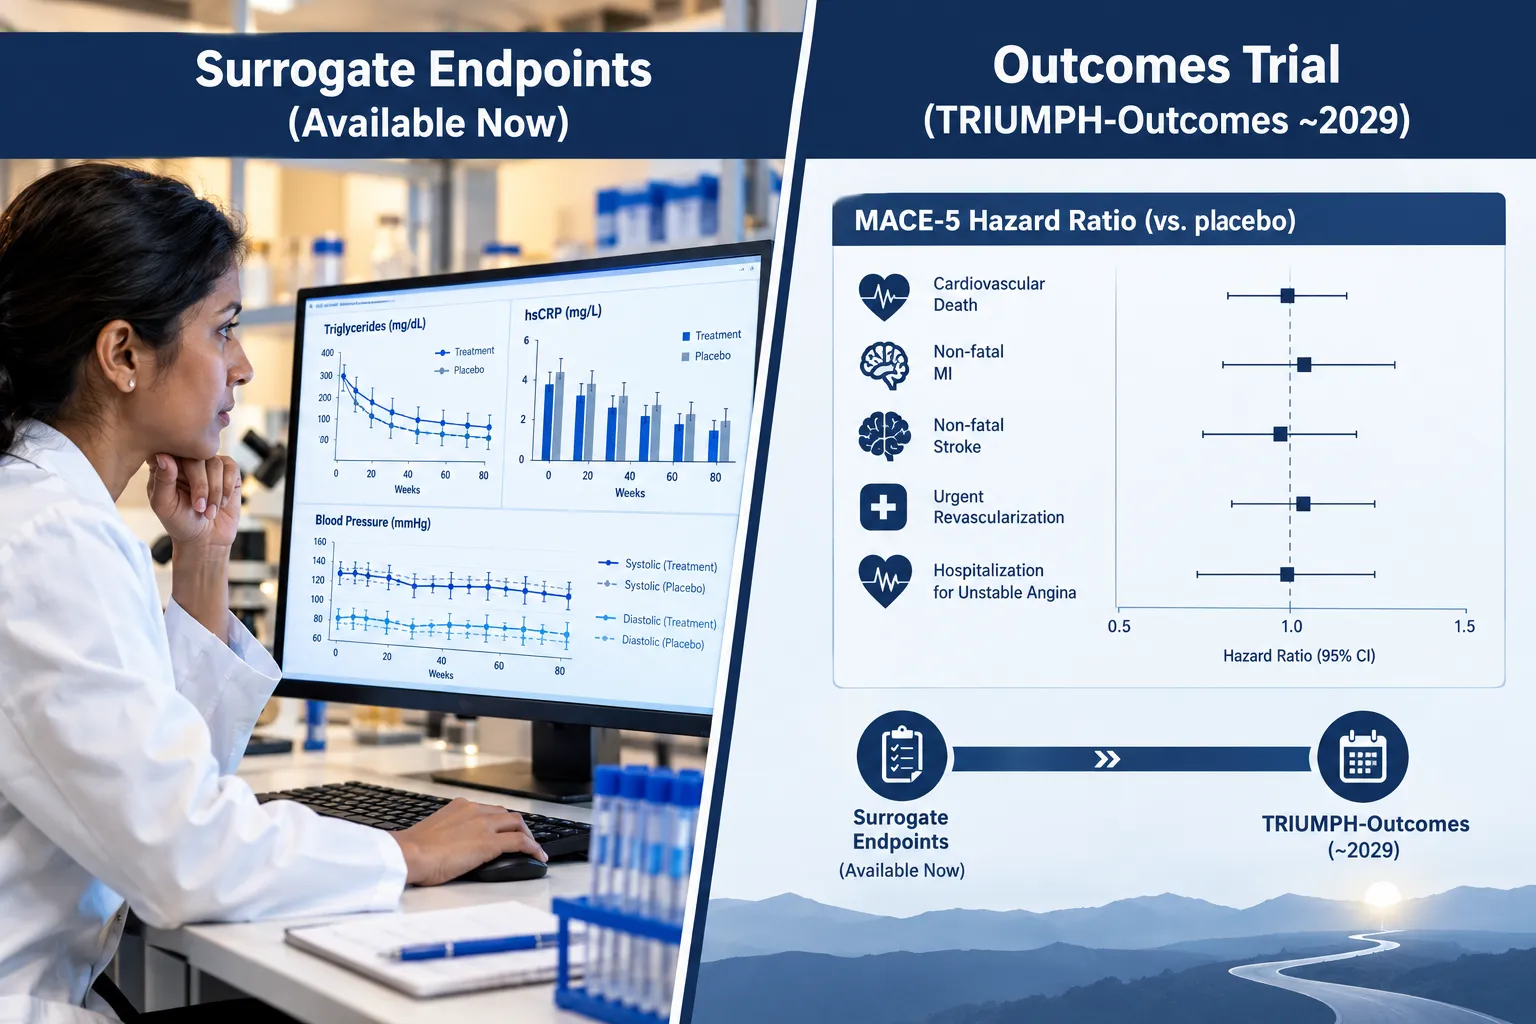
  • All four endpoints are surrogate markers, not clinical event data. The composite MACE-5 hazard ratio in TRIUMPH-3 was 0.82 but did not reach statistical significance.
  • Interpreting correlated endpoints requires understanding covariate adjustment, endpoint timing, and the distinction between weight-mediated and weight-independent effects.
  • The dedicated TRIUMPH-Outcomes cardiovascular trial is underway, with results not expected until approximately 2029 or later.

What the TRIUMPH Phase 3 Data Actually Show

The TRIUMPH program spans multiple pivotal trials. TRIUMPH-3 enrolled 1,949 adults with a BMI of 35 or higher and established cardiovascular disease. Over 80 weeks, retatrutide 12 mg delivered mean weight loss of 22.6% versus 3.2% in the control group. The cardiometabolic secondary endpoints moved in parallel:
What the TRIUMPH Phase 3 Data Actually Show

Endpoint TRIUMPH-3 (12 mg) TRIUMPH-1/TRIUMPH-4 (High Dose)
Triglycerides -37.0% -39.5%
Non-HDL Cholesterol -16.5% -19.6%
Systolic Blood Pressure -9.3 mmHg -10.8 mmHg
hsCRP -51.2% -58.3%
Waist Circumference -19.0 cm Significant reduction

In TRIUMPH-2, which studied adults with obesity or overweight and type 2 diabetes, retatrutide at 4, 9, and 12 mg produced weight losses of 12.7%, 19.1%, and 20.8%, respectively, with A1C reductions up to 1.6 percentage points. At the highest dose, systolic blood pressure fell by up to 14.0 mmHg, reinforcing that the blood pressure effect is dose-dependent and present even in a metabolically distinct population.

These findings are consistent with phase 2 data published in the NEJM, where retatrutide showed dose-dependent improvements in triglycerides, LDL cholesterol, HbA1c, and blood pressure, foreshadowing the larger phase 3 reductions across the full TRIUMPH program. Researchers following Retatrutide Clinical Trials have noted the reproducibility of these signals across different obesity phenotypes.


How to Interpret Correlated Endpoints: Separating Weight Loss from Direct Effects

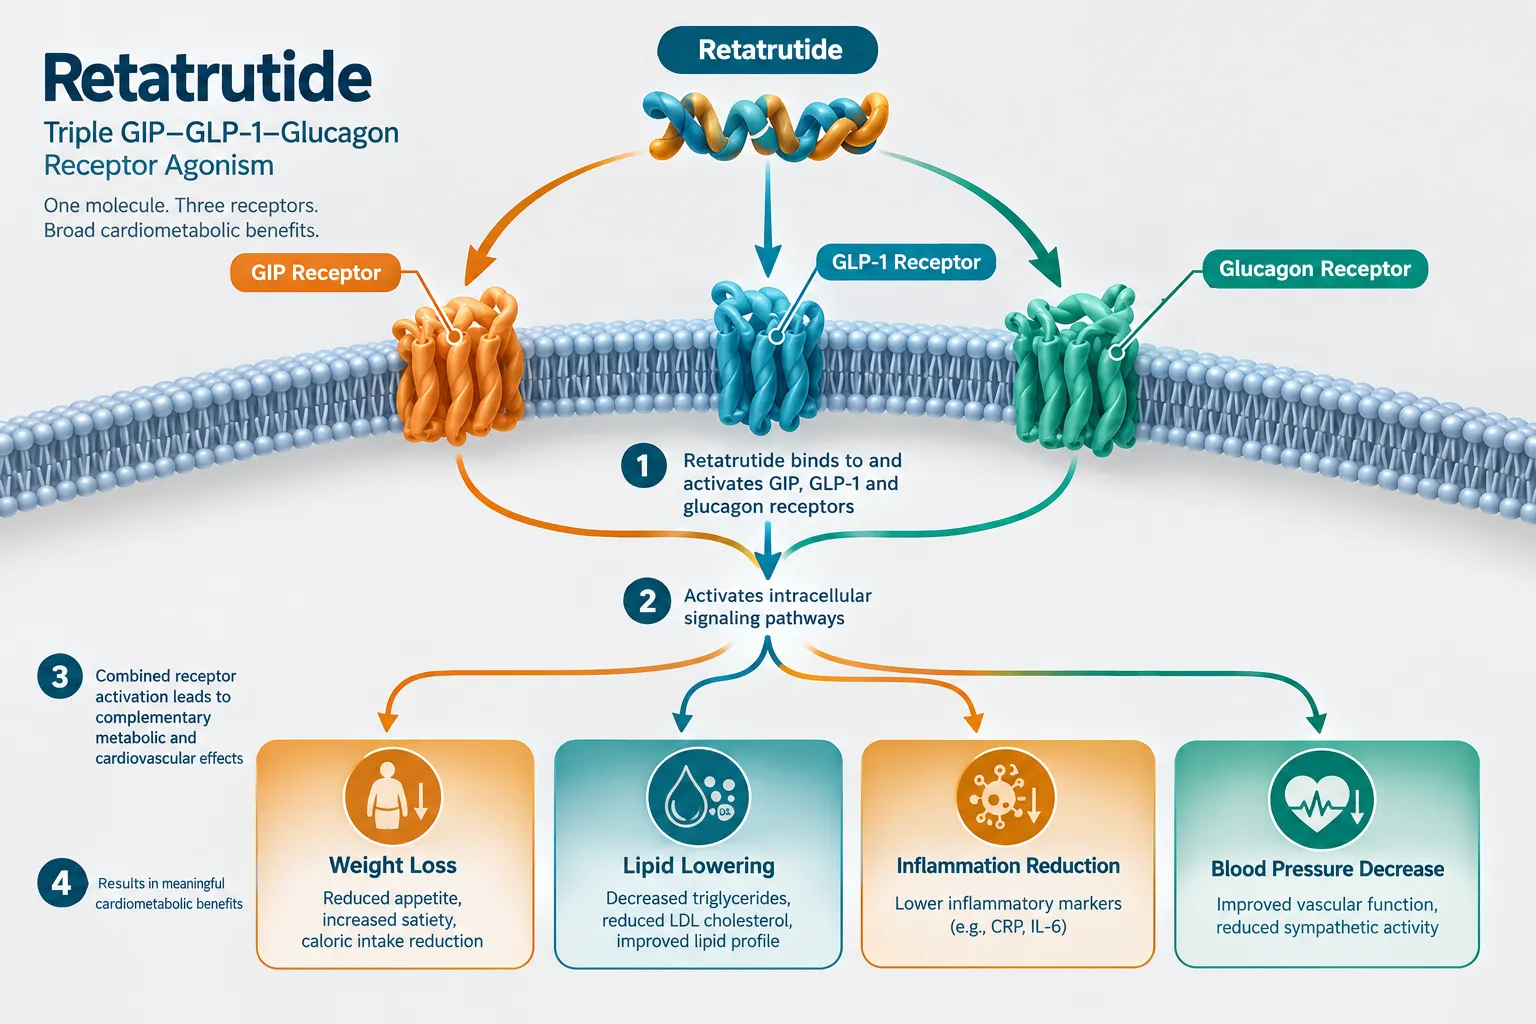
This is the central interpretive challenge in Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together. Because weight loss itself improves all four markers, it is tempting to attribute every improvement to fat mass reduction. The data suggest a more nuanced picture.
How to Interpret Correlated Endpoints: Separating Weight Loss from Direct Effects

Three interpretive principles matter here:

1. Endpoint timing relative to weight loss trajectory. Triglyceride reductions in GLP-1-class agents tend to appear early, often before peak weight loss is achieved. hsCRP reductions, by contrast, may continue to deepen as adipose-driven inflammation resolves over months. When all four endpoints are measured at the same 80-week timepoint, early and late responders are collapsed into a single number.

2. Covariate adjustment for weight change. Phase 3 secondary analyses that adjust for weight loss as a covariate can isolate the weight-independent component of each effect. Retatrutide is a triple agonist at GIP, GLP-1, and glucagon receptors. The glucagon receptor pathway has independent effects on hepatic lipid metabolism, particularly relevant to triglyceride clearance, that are not fully explained by adiposity reduction alone. Understanding GLP-1 retatrutide receptor pharmacology helps contextualize why lipid effects may exceed what weight loss alone would predict.

3. Correlation among endpoints does not imply redundancy. A patient showing large triglyceride reduction, moderate non-HDL reduction, meaningful blood pressure lowering, and substantial hsCRP reduction is experiencing improvements across three distinct cardiovascular risk axes simultaneously: atherogenic dyslipidemia, hemodynamic stress, and systemic inflammation. These are additive risk factors in atherosclerotic cardiovascular disease, and their simultaneous reduction is clinically meaningful, even before outcomes data are available.

Key distinction: Non-HDL cholesterol captures all atherogenic lipoproteins (LDL, VLDL, IDL, Lp(a)-associated particles), making it a broader risk marker than LDL alone. A 16.5% to 19.6% reduction in non-HDL represents a meaningful shift in atherogenic burden, particularly relevant in patients with residual risk despite statin therapy.


The Surrogate-to-Outcomes Gap: What the MACE Data Mean for 2026

Understanding Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together requires honest engagement with the limits of surrogate data.
The Surrogate-to-Outcomes Gap: What the MACE Data Mean for 2026

In TRIUMPH-3, the composite MACE-5 hazard ratio was 0.82 versus control. This is a numerically encouraging signal. However, it did not reach statistical significance at 80 weeks. This means retatrutide cannot yet be claimed to reduce clinical cardiovascular events, heart attacks, strokes, or cardiovascular deaths, even in a very high-risk population with established cardiovascular disease.

All cardiovascular data available as of 2026 are based on surrogate markers. The dedicated TRIUMPH-Outcomes trial is currently underway to test whether retatrutide lowers major adverse cardiovascular events in adults with overweight or obesity and established cardiovascular disease. Results are not expected until approximately 2029 or later.

What this means for interpretation:

  • Triglyceride, non-HDL, blood pressure, and hsCRP reductions are secondary endpoints in trials designed primarily around weight management and glycemic control.
  • Expert commentaries frame the multi-axis profile as targeting atherogenic lipoproteins, hemodynamic stress, and systemic inflammation simultaneously, a potentially important profile for residual cardiovascular risk.
  • Any expectation of event reduction remains speculative pending the outcomes trial.
  • If TRIUMPH-Outcomes demonstrates meaningful MACE reduction, formal cardiovascular risk-reduction labeling would likely not be possible before the early 2030s.

Researchers tracking Retatrutide Clinical Trial developments should note that the consistency of surrogate endpoint data across TRIUMPH-1, TRIUMPH-2, TRIUMPH-3, and TRIUMPH-4 strengthens confidence in the reliability of these secondary findings, even as the outcomes question remains open. Those interested in the combination pipeline can also review data on Cagrilintide and Retatrutide for context on next-generation cardiometabolic approaches.


Conclusion

The TRIUMPH phase 3 program has produced one of the most comprehensive cardiometabolic secondary endpoint datasets in obesity pharmacology to date. Triglycerides falling 37-39%, non-HDL cholesterol declining 16-20%, systolic blood pressure dropping 9-14 mmHg, and hsCRP reducing by more than half, all at 80 weeks, represent a reproducible, multi-axis cardiometabolic signal across different obesity phenotypes and comorbidity profiles.

Actionable next steps for researchers and clinicians reviewing this data:

  • Examine covariate-adjusted analyses that isolate weight-independent lipid and inflammatory effects before attributing all improvement to fat mass reduction.
  • Treat the four endpoints as complementary axes, not redundant measures, each captures a distinct cardiovascular risk pathway.
  • Apply appropriate interpretive caution: surrogate improvements do not confirm event reduction until TRIUMPH-Outcomes reports.
  • Monitor Eli Lilly's ongoing regulatory submissions and TRIUMPH-Outcomes enrollment milestones, expected to be decisive around 2029.

The cardiometabolic profile of retatrutide is now a central part of its value proposition, not an exploratory footnote. Reading it correctly, with attention to endpoint timing, covariate structure, and the surrogate-to-outcomes gap, is essential for any rigorous assessment of this triple agonist's place in cardiovascular risk management.


https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-cardiometabolic-endpoints-how-to-interpret-triglycerides-non.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-08 13:12:122026-10-08 13:12:12Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together
Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C

Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C

October 3, 2026/0 Comments/in Uncategorized/by

"

Professional () hero image with 'Retatrutide and Cardiovascular Disease' in crisp white on a deep navy semi-transparent

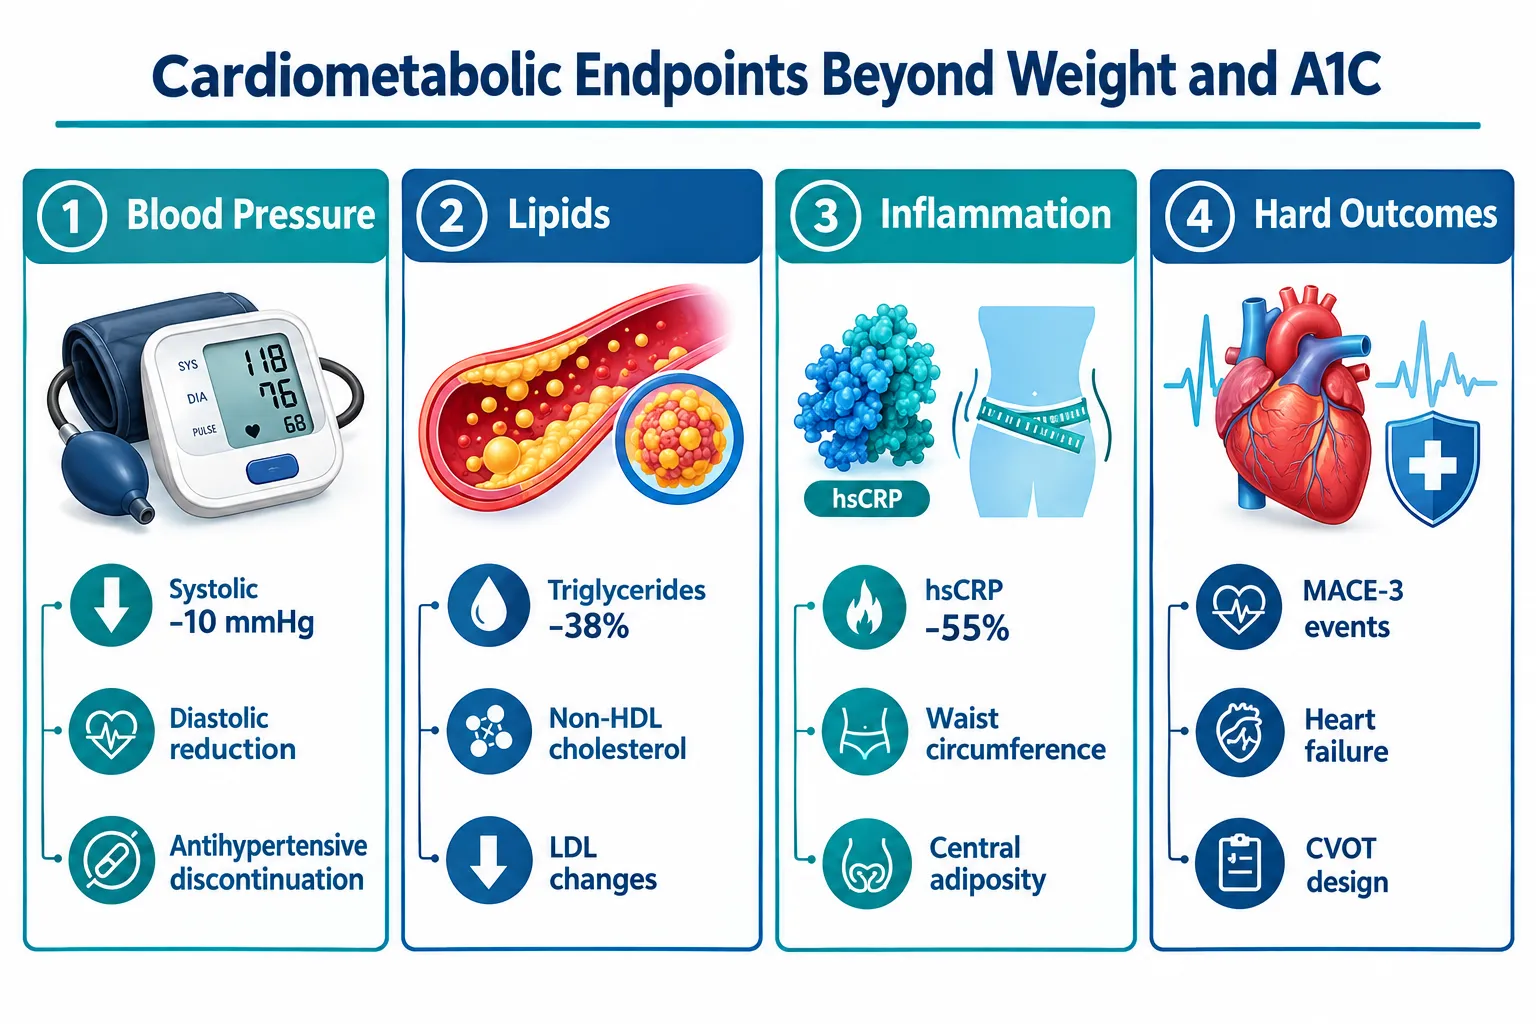
Cardiovascular disease kills more people with obesity and type 2 diabetes than any other complication, yet most obesity drug trials still define success almost entirely by the number on a scale or a single blood sugar marker. Retatrutide and cardiovascular disease research is now forcing a rethink of that narrow framework, pushing investigators to design endpoints that capture blood pressure, lipid profiles, inflammatory biomarkers, and hard cardiovascular events alongside weight and A1C.

Key Takeaways

  • Retatrutide, a GLP-1/GIP/glucagon triple agonist, produces striking reductions in blood pressure, triglycerides, waist circumference, and high-sensitivity C-reactive protein (hsCRP), signals that go well beyond weight loss and glycemic control.
  • Phase 3 TRIUMPH-3 data showed roughly 22-25% weight reduction at 12 mg, with systolic blood pressure falling up to 10.8 mmHg and hsCRP dropping up to 58%, but cardiovascular event rates did not reach statistical significance.
  • A dedicated cardiovascular outcomes trial (CVOT) is underway, designed specifically to evaluate major adverse cardiovascular events (MACE) in high-risk populations.
  • Distinguishing exploratory cardiometabolic signals from validated cardiovascular-outcome evidence is essential for sound protocol planning and regulatory strategy.
  • Future endpoint frameworks will likely use integrated cardiometabolic composites, covering lipids, inflammation, central adiposity, and organ-specific outcomes, rather than relying on weight and A1C alone.

Why Triple-Agonist Biology Demands Broader Endpoint Thinking

Why Triple-Agonist Biology Demands Broader Endpoint Thinking

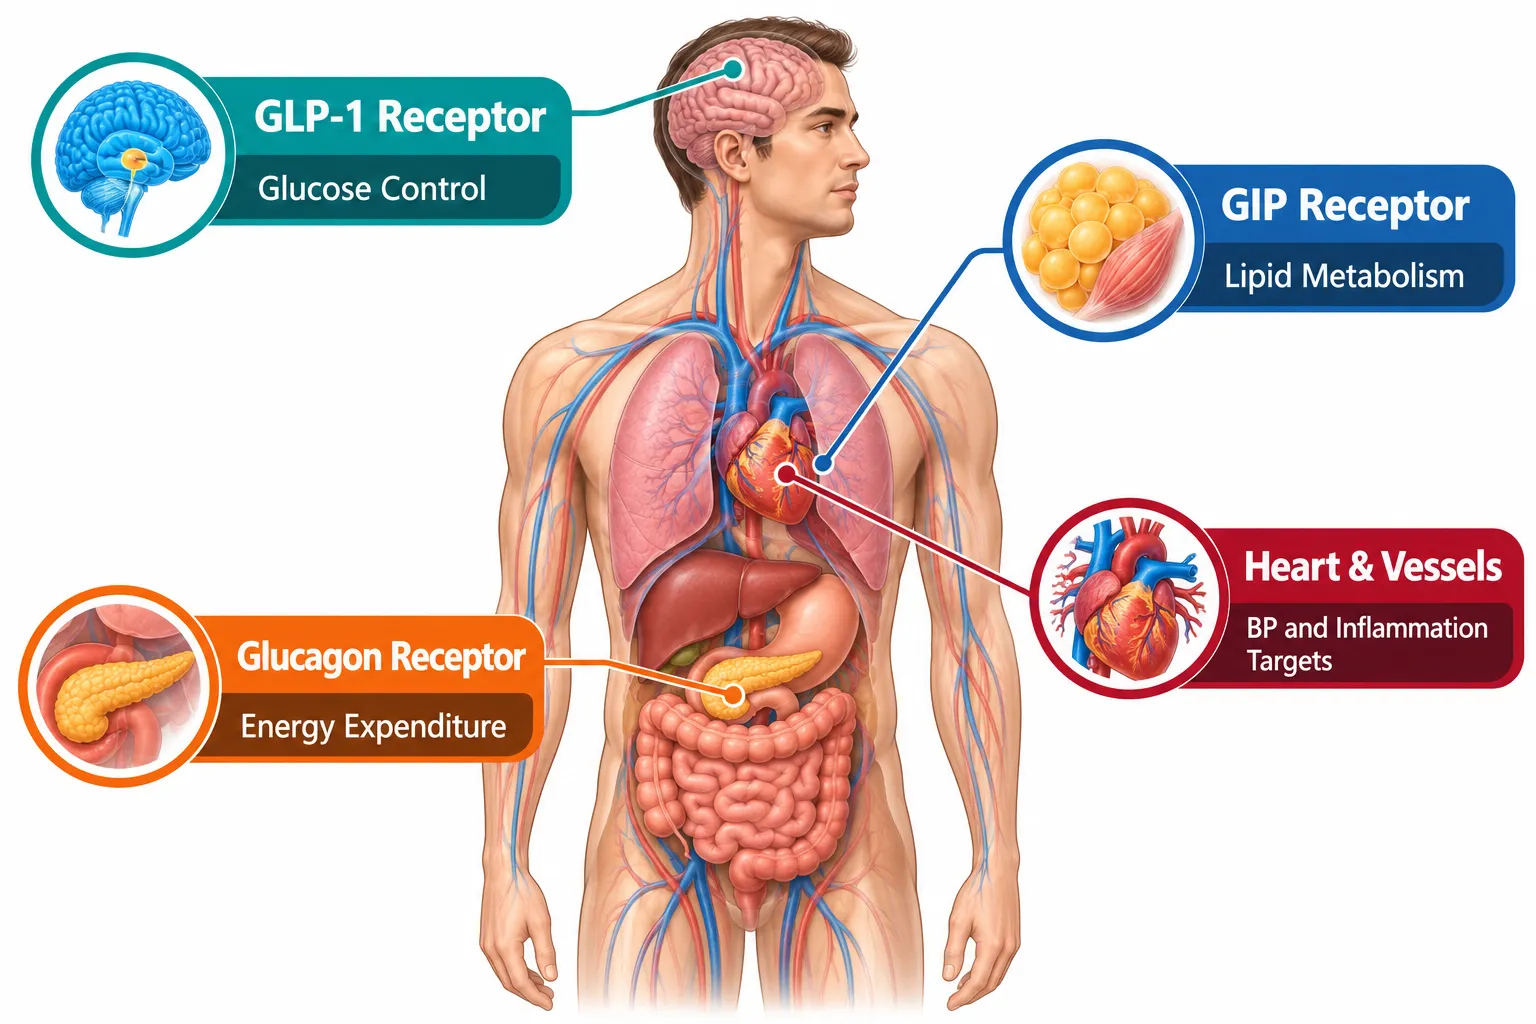
Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, a pharmacological profile that creates metabolic effects across multiple organ systems at once. This broad reach is precisely why retatrutide clinical trials have moved quickly to incorporate cardiometabolic measures as prespecified exploratory endpoints rather than afterthoughts.

In the pivotal phase 2 obesity trial published in the New England Journal of Medicine, once-weekly retatrutide produced a mean weight reduction of 24.2% at 48 weeks at higher doses. Alongside that headline figure, investigators tracked systolic and diastolic blood pressure, waist circumference, fasting glucose, insulin, glycated hemoglobin, and most lipid parameters. That multi-factor design reflected an early recognition that glucagon receptor agonism affects hepatic lipid metabolism and energy expenditure in ways that GLP-1 alone does not.

A 2024 meta-analysis confirmed statistically significant reductions in systolic blood pressure (pooled weighted mean difference of approximately -4.70 mmHg) and diastolic blood pressure (-1.73 mmHg) across retatrutide studies. Complementary Lancet data showed systolic blood pressure falling roughly 5 mmHg with active doses versus about 1.5 mmHg on placebo over 40 weeks. These consistent signals across studies support blood pressure as a reliable intermediate endpoint, one that is biologically plausible, measurable, and clinically meaningful.

Protocol planning note: Blood pressure and lipid changes are reproducible across retatrutide studies, making them strong candidates for secondary or co-primary endpoints in future trials. They should not be treated as incidental observations.

Researchers designing studies around GLP-1 Reta compounds increasingly recognize that a single surrogate endpoint misrepresents the drug's full cardiometabolic footprint.


Cardiometabolic Endpoint Design: From Signals to Evidence

Cardiometabolic Endpoint Design: From Signals to Evidence

The TRIUMPH-3 phase 3 trial, which enrolled nearly 2,000 adults with severe obesity (BMI 35 or higher) and established cardiovascular disease, generated the most comprehensive cardiometabolic endpoint data to date. Results released in late September 2026 showed the following at the highest 12 mg dose:

Endpoint Approximate Change vs. Placebo
Systolic blood pressure -9.3 to -10.8 mmHg
Triglycerides -37 to -39.5%
Non-HDL cholesterol -16.5 to -19.6%
Waist circumference -16.9 to -19.0 cm
hsCRP -51 to -58%

These figures represent a multi-dimensional risk-modification profile that no single endpoint could capture. The hsCRP reduction in particular is notable: chronic low-grade inflammation is an independent cardiovascular risk factor, and a 51-58% drop in this marker suggests retatrutide may be modifying vascular biology beyond what weight loss alone would explain.

Equally important is the medication-burden signal. In the NEJM phase 2 trial, 41% of patients in the 8 mg group and 30% in the 12 mg group were able to discontinue at least one antihypertensive medication. This is a clinically relevant endpoint that regulatory agencies and payers increasingly value, it reflects real-world health impact, not just a surrogate number.

However, a critical distinction must be made. Despite these striking risk-factor improvements, TRIUMPH-3 did not show statistically significant reductions in major cardiovascular events. There were 44 MACE-5 events in the retatrutide group versus 52 in the placebo group, yielding a hazard ratio of 0.82 (95% CI 0.55-1.22). The MACE-3 hazard ratio was 1.12 (95% CI 0.64-1.96). The trial was not powered to detect event-level differences, and event counts were lower than projected. This is the essential gap between exploratory cardiometabolic signals and validated cardiovascular-outcome evidence.

For researchers working with related peptide frameworks such as SS-31 mitochondrial research or tesa dosage for fat loss protocols, this distinction between surrogate improvements and hard event outcomes is a recurring methodological challenge across the field.


Designing the Next Generation of Retatrutide Cardiovascular Endpoints

Designing the Next Generation of Retatrutide Cardiovascular Endpoints

A dedicated CVOT for retatrutide is now underway, targeting adults with overweight or obesity and established cardiovascular disease. This trial is explicitly designed to answer the question that TRIUMPH-3 could not: does retatrutide reduce major adverse cardiovascular events at a statistically powered level?

Recommended endpoint architecture for future retatrutide CVOTs:

  • Primary endpoint: MACE-3 (cardiovascular death, non-fatal myocardial infarction, non-fatal stroke) as the regulatory standard
  • Key secondary endpoints: Heart failure hospitalizations, kidney function trajectories, all-cause mortality
  • Exploratory biomarker endpoints: hsCRP, NT-proBNP, albuminuria, imaging-based myocardial structure measures
  • Safety hemodynamic monitoring: Pulse rate, arrhythmia surveillance, autonomic function, early diabetes studies showed increased pulse rate despite lower blood pressure, underscoring the need for comprehensive hemodynamic tracking

The inflammatory marker data from TRIUMPH-3 strengthens the case for including hsCRP and other inflammatory endpoints as prespecified secondary measures. A 51-58% reduction in hsCRP is not a minor signal; it warrants formal hypothesis testing in a powered trial.

Renal outcomes deserve explicit attention given the overlap between obesity, type 2 diabetes, and chronic kidney disease in high-risk populations. Albuminuria and estimated glomerular filtration rate trajectories should be incorporated as secondary endpoints, consistent with the approach taken in GLP-1 CVOT designs. For context on how related peptide research approaches multi-system endpoints, the GLP3 Reta compound research framework offers a useful parallel.

Lilly's March 2026 release on retatrutide in people with obesity and type 2 diabetes explicitly framed non-HDL cholesterol, triglyceride, and blood pressure improvements as key differentiating endpoints alongside glycemic control, signaling that the company's own endpoint strategy has already moved beyond weight and A1C.


Conclusion

Retatrutide and cardiovascular disease research is at a pivotal inflection point in 2026. The cardiometabolic signal is strong: blood pressure reductions of up to 10.8 mmHg, triglyceride drops approaching 40%, hsCRP reductions exceeding 50%, and clinically meaningful antihypertensive medication discontinuation rates all point to a drug with broad cardiovascular risk-modification potential.

What the evidence does not yet support is a validated claim of cardiovascular event reduction. TRIUMPH-3 was not powered for that conclusion, and the ongoing CVOT must deliver that answer before a formal cardiovascular risk-reduction indication can be pursued.

Actionable next steps for protocol designers and researchers:

  1. Build composite cardiometabolic endpoints into study designs from the start, do not treat blood pressure, lipids, and inflammation as secondary afterthoughts.
  2. Power dedicated CVOTs specifically for MACE, not just for weight loss, and include heart failure and renal outcomes as key secondary endpoints.
  3. Monitor hemodynamic safety comprehensively, including pulse rate and arrhythmia surveillance, given the mixed blood pressure and heart rate signals seen in early studies.
  4. Use inflammatory biomarkers such as hsCRP as prespecified exploratory endpoints to build the evidence base for future mechanistic claims.
  5. Follow retatrutide clinical trials progress closely, as CVOT results will determine whether the robust risk-factor improvements seen to date translate into the event-level cardiovascular benefit that patients and regulators require.

The science is compelling. The endpoint design must now match the ambition of the biology.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-and-cardiovascular-disease-research-designing-endpoints-beyond-weigh.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-03 13:04:482026-10-03 13:04:48Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top