Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: calcium-channel blocker

Amlodipine in Peptide Research: Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts

Amlodipine in Peptide Research: Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts

October 6, 2026/0 Comments/in Uncategorized/by

Fewer than one in five preclinical peptide studies that co-administer a calcium-channel blocker formally account for the drug's independent vascular effects, a methodological gap that can quietly invalidate entire datasets. When amlodipine in peptide research enters the experimental picture, the challenge is not simply adjusting for lower blood pressure. It is disentangling at least three overlapping biological layers: direct L-type calcium-channel blockade, blood-pressure-dependent vascular changes, and blood-pressure-independent vascular remodeling. Getting these layers wrong means attributing amlodipine's known anti-proliferative and anti-atherosclerotic actions to the peptide under study, or, just as problematically, masking a real peptide signal behind the drug's dominant pharmacology.

Key Takeaways

  • Amlodipine blocks L-type calcium channels in vascular smooth muscle, reducing intracellular Ca²⁺ and causing arterial relaxation independently of any peptide co-administered in a study.
  • The drug produces vascular benefits, including inhibited smooth-muscle cell proliferation and slowed atherosclerosis, that are separate from its blood-pressure-lowering effect.
  • At clinically relevant concentrations, amlodipine does not activate CRAC channels and does not interfere with fluorescence-based Ca²⁺ imaging dyes such as Cal-520, Fluo-4, or Fura-Red.
  • Researchers should pre-specify which readouts are calcium-channel-mediated, blood-pressure-dependent, or peptide-specific before data collection begins.
  • Orthogonal biomarkers, endothelial nitric oxide, arterial compliance, and vascular remodeling indices, can help isolate a peptide's contribution from amlodipine's background pharmacology.

How Amlodipine Works: The Calcium-Channel Mechanism Researchers Must Account For
How Amlodipine Works: The Calcium-Channel Mechanism Researchers Must Account For

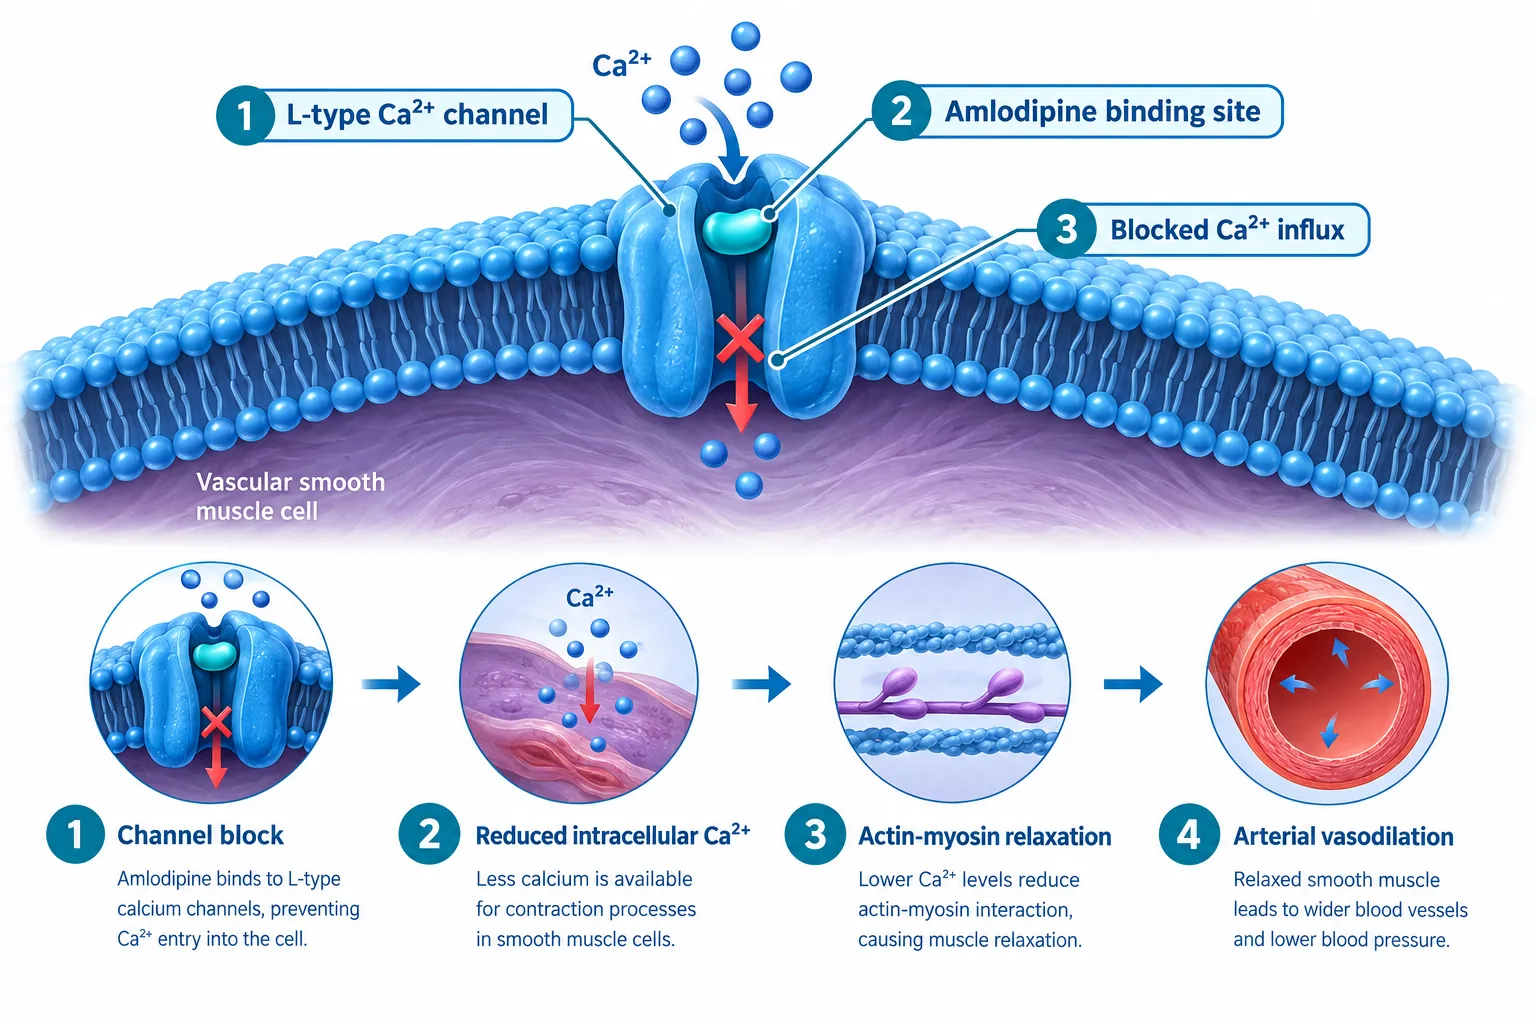
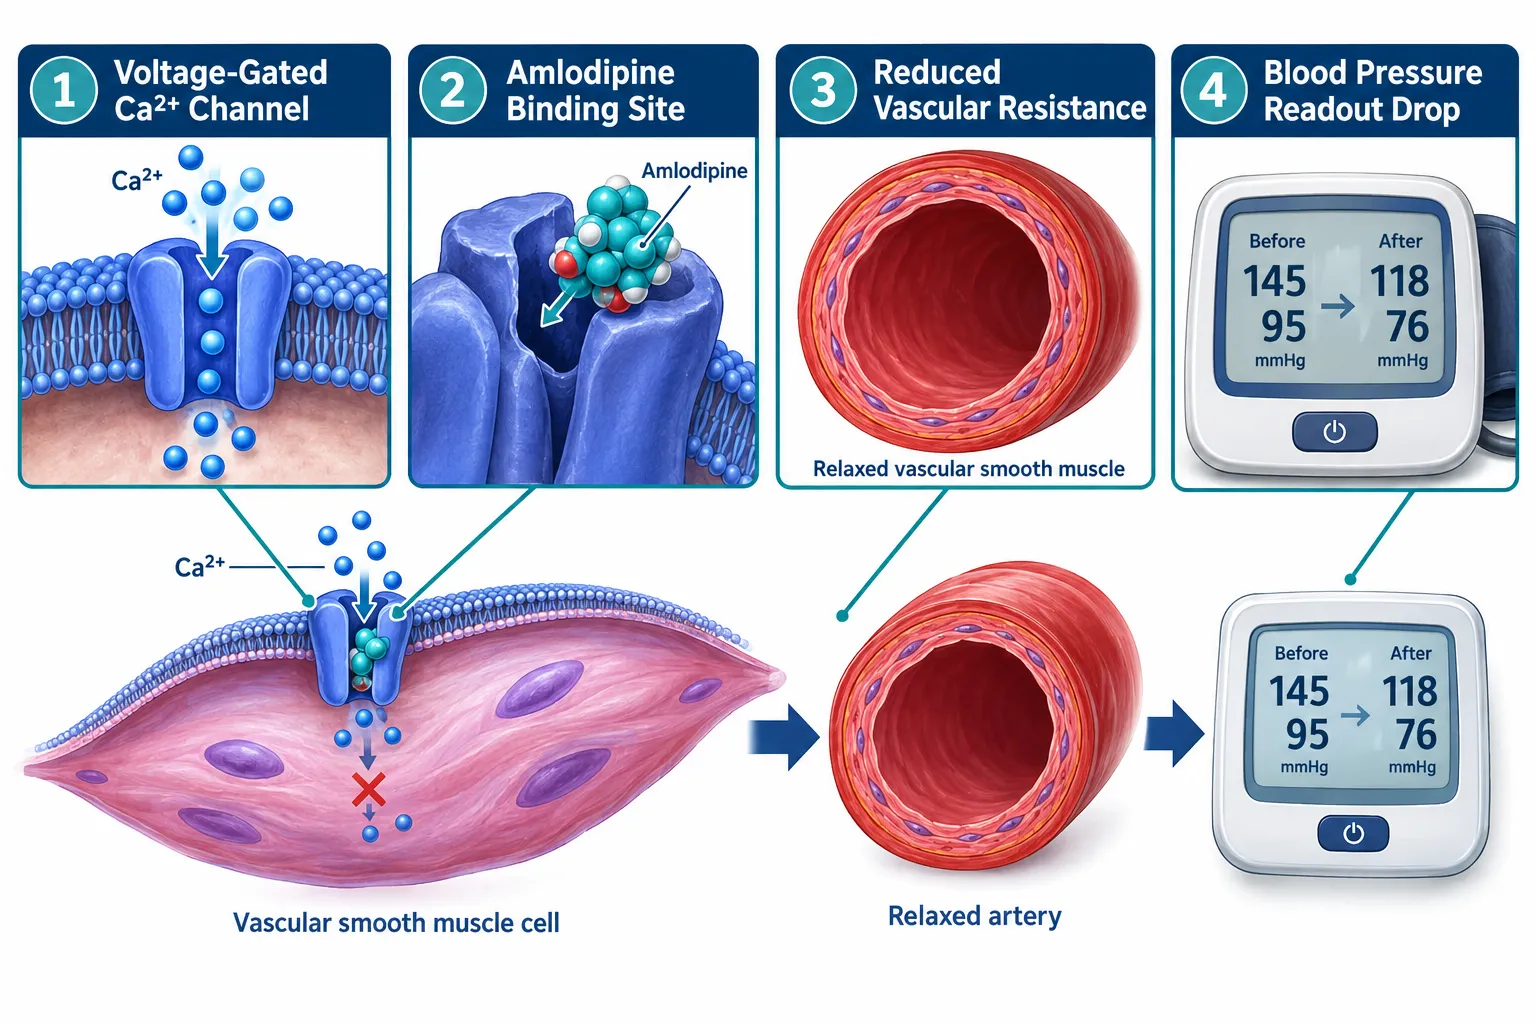
Amlodipine is a dihydropyridine calcium antagonist. Its primary action is inhibiting the transmembrane influx of calcium ions through L-type voltage-gated channels, predominantly in vascular smooth muscle cells. The result is reduced intracellular Ca²⁺, diminished actin-myosin interaction, smooth-muscle relaxation, and arterial vasodilation. Its effect on vascular smooth muscle is substantially greater than its effect on cardiac muscle, a selectivity profile that matters when interpreting any cardiovascular or vascular readout in a peptide experiment.

This mechanism is not trivial background noise. It is a dominant pharmacological signal. Any peptide co-administered with amlodipine that also influences vascular tone, intracellular calcium, or smooth-muscle behavior will generate data that reflects both agents simultaneously unless the study design explicitly separates them.

What this means practically:

  • Vascular tone measurements (e.g., wire myography, pressure myography) will reflect amlodipine's baseline relaxation effect.
  • Intracellular Ca²⁺ flux assays will show a suppressed resting Ca²⁺ level before the peptide is even introduced.
  • Any peptide with vasodilatory properties may appear to have a blunted or absent effect simply because the vascular bed is already partially relaxed.

Researchers working with mitochondria-targeted peptides such as those explored in SS-31 10mg research peptide considerations should note that oxidative-stress and membrane-potential readouts can also be indirectly affected when intracellular calcium homeostasis is altered by a co-administered channel blocker.


Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts: A Practical Framework
Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts: A Practical Framework

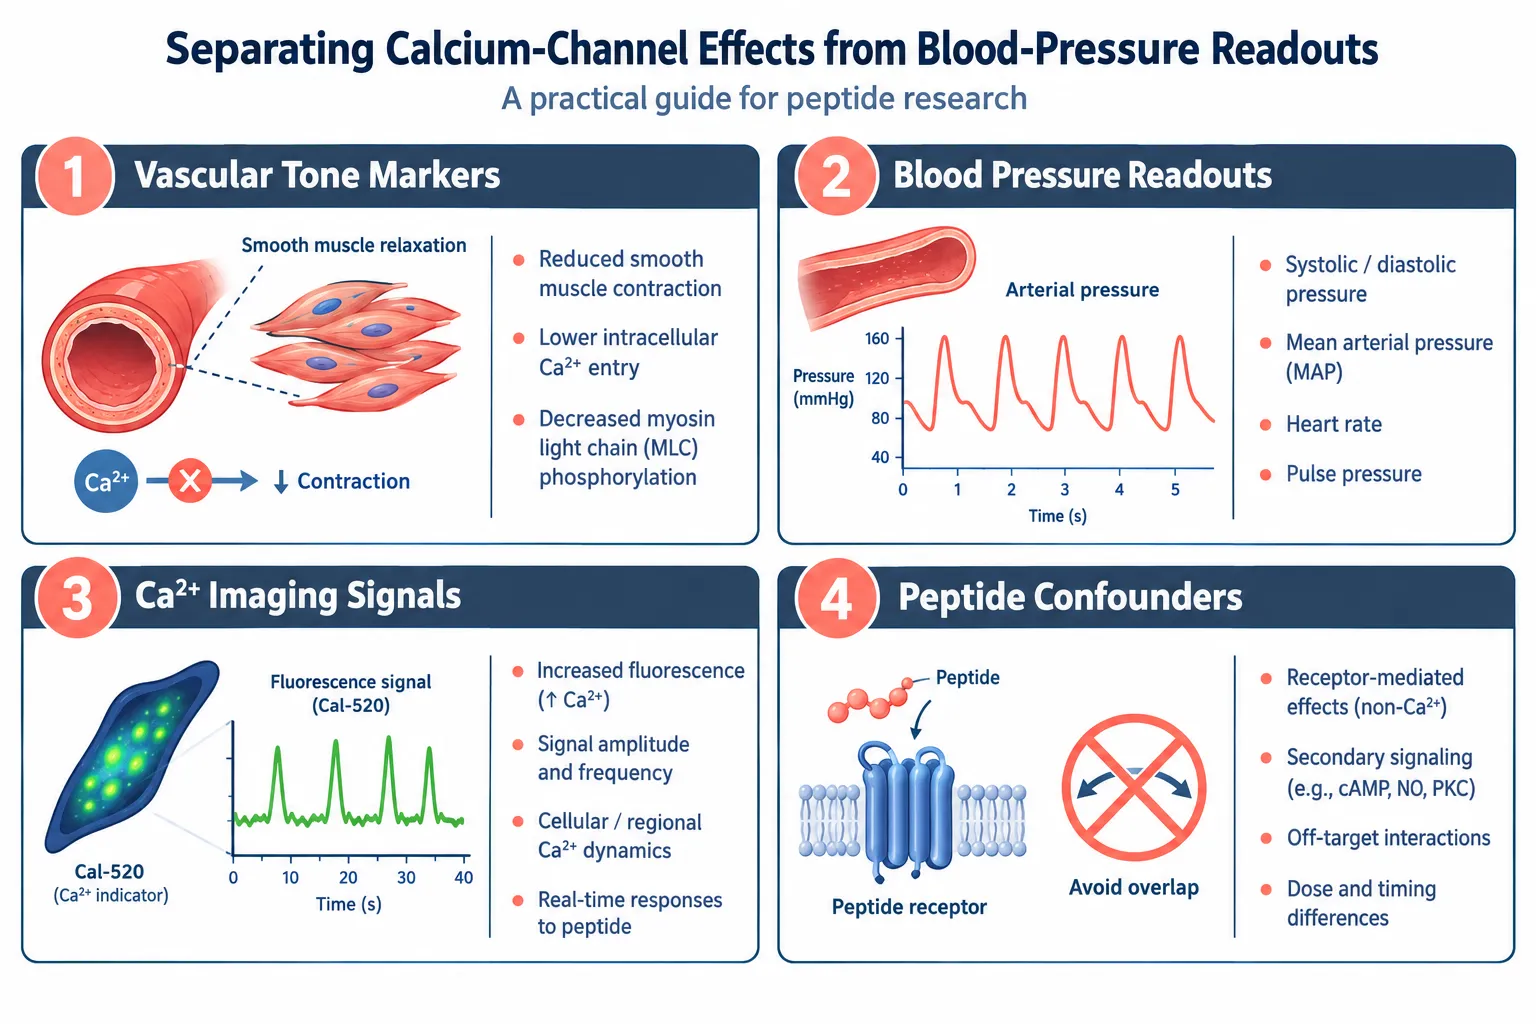
The central challenge in amlodipine in peptide research, separating calcium-channel effects from blood-pressure and vascular readouts, requires a tiered classification of every endpoint before data collection begins.

Tier 1: Blood-Pressure-Dependent Readouts

These are endpoints that change because amlodipine lowers arterial pressure. They include:

  • Brachial or carotid blood pressure values
  • Cardiac afterload indices
  • Glomerular filtration rate changes driven by reduced perfusion pressure

Practical step: Include a vehicle-treated, amlodipine-only control group at the same dose. Any change in these readouts in that group represents the amlodipine baseline, not a peptide effect.

Tier 2: Blood-Pressure-Independent Vascular Effects

Contemporary cardiovascular literature consistently identifies a second category of amlodipine actions that persist even when blood pressure is matched to comparator agents. These include:

Effect Mechanism Research Implication
Smooth-muscle cell anti-proliferation Direct Ca²⁺ signaling suppression May confound peptide anti-proliferative claims
Anti-atherosclerotic remodeling Reduced oxidative stress in vessel wall Arterial stiffness data needs amlodipine-only control
Improved arterial compliance Structural vascular changes Central pulse-wave velocity requires correction

For peptide studies examining vascular remodeling, such as those involving VIP peptide mechanisms or vasoactive signaling pathways, these BP-independent effects represent the most likely source of confounding.

Tier 3: Calcium-Channel-Specific Molecular Readouts

This tier covers direct molecular measurements of L-type channel activity and downstream Ca²⁺ signaling. A key methodological advantage here: at therapeutic plasma concentrations of approximately 0.5 µM, amlodipine does not activate calcium-release-activated calcium (CRAC) channels. This means CRAC-mediated signaling events attributed to a peptide are not being driven by amlodipine itself.

Additionally, fluorescence-based Ca²⁺ imaging using dyes such as Cal-520, Fluo-4, and Fura-Red is not confounded by amlodipine fluorescence at these concentrations. This is a meaningful green light for researchers using live-cell calcium imaging alongside peptide stimulation assays.

"Knowing which calcium compartment amlodipine does and does not touch is the single most useful piece of information a peptide researcher can carry into experimental design."

Researchers examining peptide signaling pathways, including those studying GLP-3 peptide signaling pathway interactions, benefit from this CRAC-channel clarity because receptor-operated calcium entry can then be attributed with greater confidence to the peptide's receptor engagement rather than to the channel blocker.


Designing the Experiment: Isolating Peptide-Specific Signals
Designing the Experiment: Isolating Peptide-Specific Signals

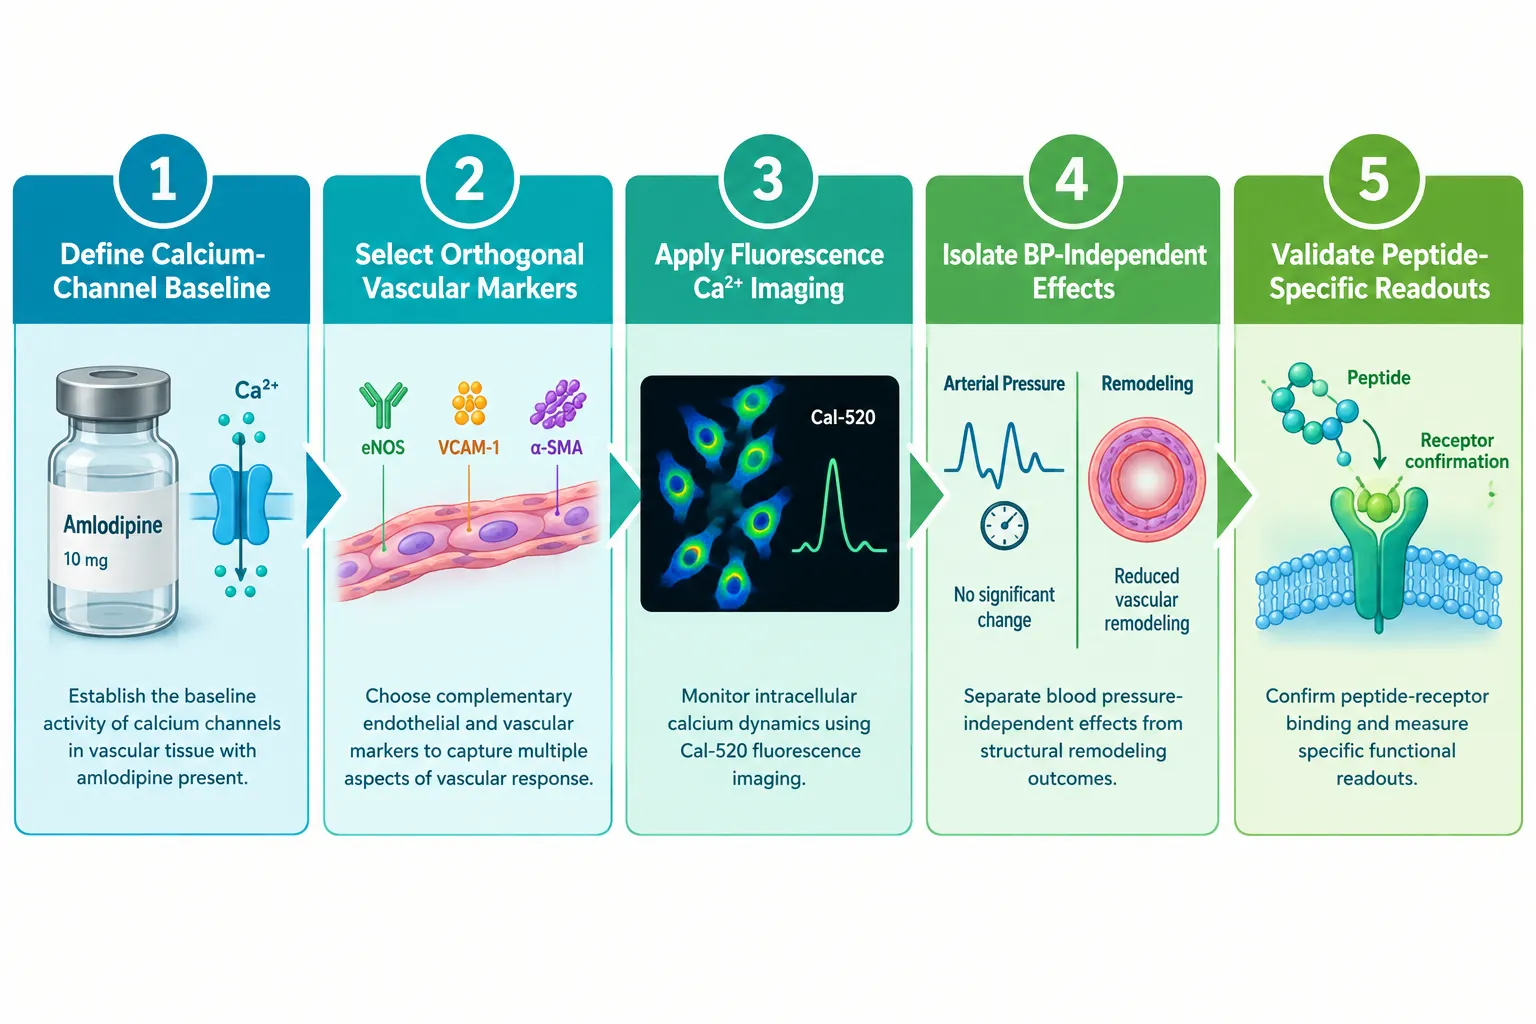
A rigorous experimental framework for amlodipine in peptide research, one that genuinely separates calcium-channel effects from blood-pressure and vascular readouts, involves five concrete design decisions.

Step 1, Define the calcium-channel baseline. Run amlodipine-only controls at the intended study concentration. Measure intracellular Ca²⁺, vascular tone, and any remodeling markers. This establishes the floor the peptide must be measured against.

Step 2, Select orthogonal vascular markers. Choose at least two endpoints that amlodipine does not directly regulate. Endothelial nitric oxide synthase (eNOS) activity, circulating endothelin-1 levels, and specific peptide receptor phosphorylation states are examples. These serve as peptide-specific signal channels.

Step 3, Apply fluorescence Ca²⁺ imaging with confidence. Given that amlodipine does not interfere with Cal-520, Fluo-4, or Fura-Red at relevant concentrations, live-cell imaging remains a valid tool. Pair it with a CRAC-channel inhibitor control to confirm that any observed Ca²⁺ flux is L-type-independent when the peptide is active.

Step 4, Separate central from peripheral blood pressure. Peripheral brachial pressure can be identical across treatment groups while central aortic pressure and pulse-wave velocity differ. Use central hemodynamic measurements to capture amlodipine's BP-independent arterial effects separately from peptide-driven changes.

Step 5, Validate with receptor-blocking controls. If the peptide of interest acts through a specific receptor, as is the case with many research peptides including those reviewed in LL-37 versus SS-31 benefits of each peptide comparisons, include a receptor-antagonist arm. Any vascular effect that disappears with receptor blockade but persists with amlodipine alone is attributable to the peptide.

Proper peptide dosing protocols also matter here: dose-response curves for the peptide should be generated in both the presence and absence of amlodipine to detect any shift in potency or efficacy caused by the background calcium-channel blockade.

For researchers sourcing compounds for controlled in vitro work, ensuring purity and verified composition is non-negotiable. Resources such as guidance on where to buy research-grade peptides evaluating purity underscore why compound quality directly affects the reliability of mechanistic conclusions.


Conclusion

Amlodipine is a well-characterized L-type calcium-channel blocker with a pharmacological footprint that extends well beyond simple blood-pressure reduction. In any peptide research context, failing to account for its anti-proliferative, anti-atherosclerotic, and Ca²⁺-suppressive actions risks misattributing drug effects to the peptide, or obscuring genuine peptide biology beneath a dominant pharmacological background.

Actionable next steps for researchers in 2026:

  1. Pre-classify every planned endpoint into one of the three tiers: blood-pressure-dependent, BP-independent vascular, or calcium-channel-specific molecular.
  2. Include an amlodipine-only control group at the study concentration in every experimental arm.
  3. Use fluorescence-based Ca²⁺ imaging with confidence at therapeutic concentrations, but pair it with CRAC-channel controls to confirm the signal source.
  4. Add orthogonal endothelial and receptor-specific biomarkers that amlodipine does not directly regulate.
  5. Run full dose-response curves for the peptide both with and without amlodipine present to detect potency shifts.

Rigorous separation of these layers does not complicate peptide research, it protects it. The result is data that can be defended, reproduced, and built upon.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/amlodipine-in-peptide-research-separating-calcium-channel-effects-from-blood-pre.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-06 13:05:532026-10-06 13:05:53Amlodipine in Peptide Research: Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts
Amlodipine and Research Peptides: How Calcium-Channel Blockade Can Confound Blood-Pressure Experiments

Amlodipine and Research Peptides: How Calcium-Channel Blockade Can Confound Blood-Pressure Experiments

October 4, 2026/0 Comments/in Uncategorized/by

Fewer than 10% of preclinical cardiovascular studies explicitly report whether test subjects were receiving background antihypertensive therapy, yet a single oral dose of amlodipine can drop systolic blood pressure by 18 to 45 mmHg for six hours or longer. That gap between standard practice and methodological rigor sits at the heart of the problem explored here. Understanding Amlodipine and Research Peptides: How Calcium-Channel Blockade Can Confound Blood-Pressure Experiments is not a niche concern; it is a prerequisite for any researcher using GLP-class peptides, growth-hormone secretagogues, or tissue-repair compounds in models where blood pressure, vascular tone, or intracellular calcium is a primary endpoint.

Key Takeaways

  • Amlodipine produces dose-dependent, long-lasting blood-pressure reductions that can dominate hemodynamic readouts across typical experimental windows.
  • Calcium-channel blockade can physically interfere with fura-based fluorescent calcium imaging, producing false signals that mimic peptide activity.
  • Circadian blood-pressure patterns, critical for ambulatory monitoring studies, can be altered by amlodipine independently of any peptide intervention.
  • Confounding by indication and dose is a recognized methodological hazard in pharmacoepidemiology that applies directly to peptide trials.
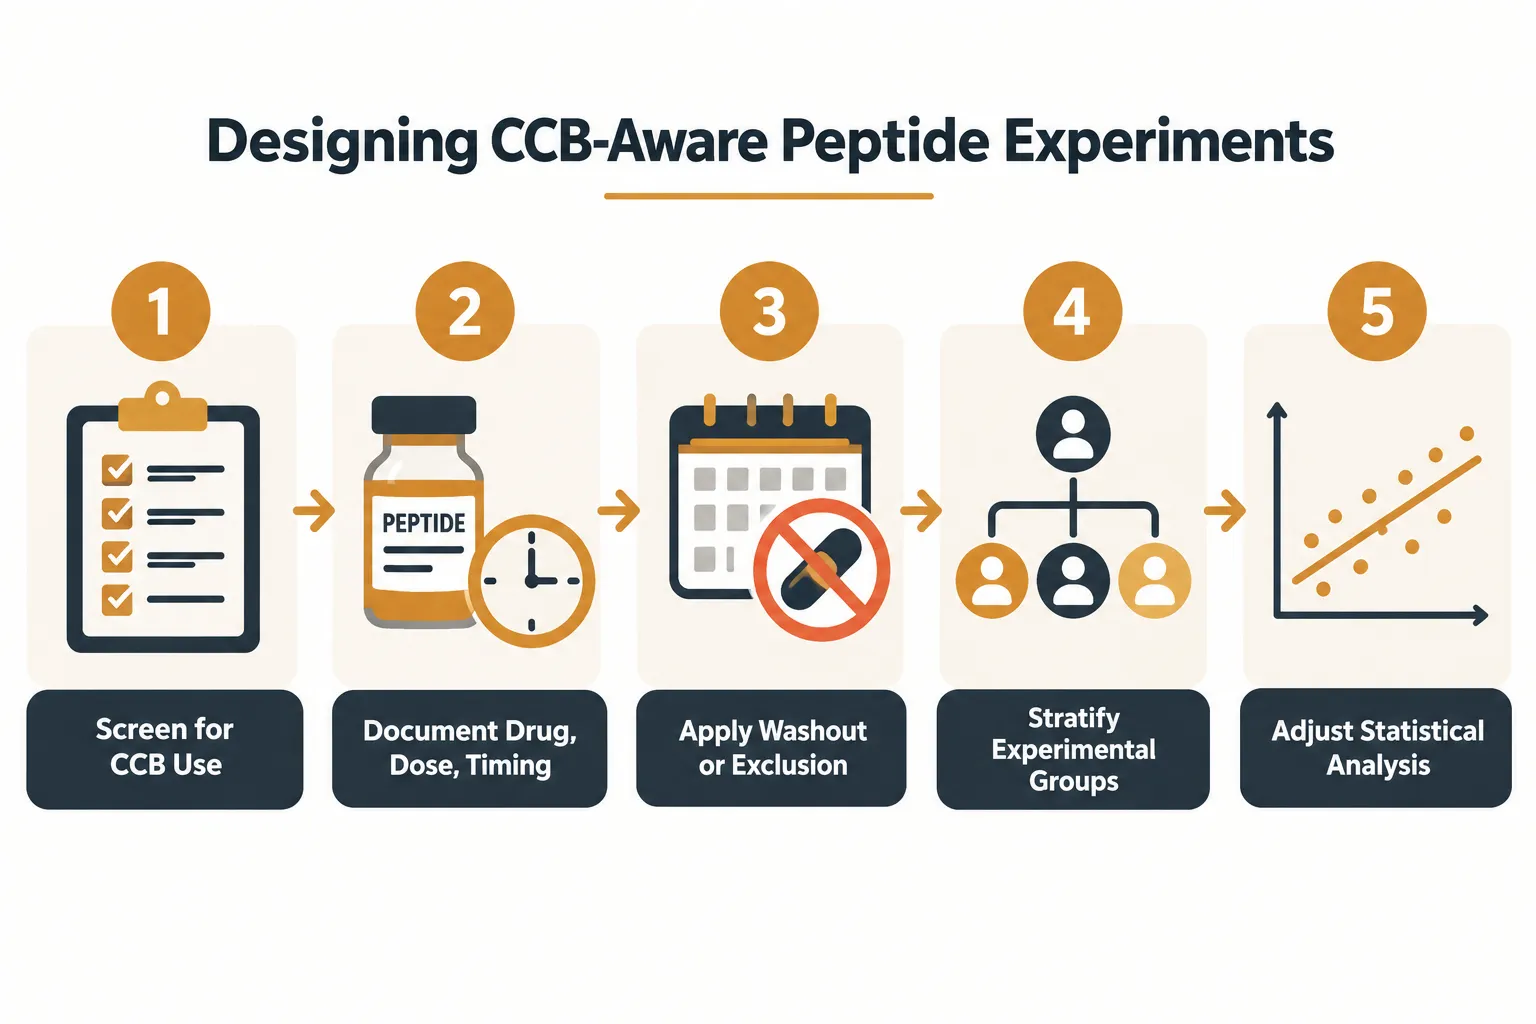
  • Researchers can control for these effects through explicit CCB documentation, adequate washout periods, group stratification, and adjusted statistical models.

How Amlodipine Changes Vascular Tone and Blood-Pressure Baselines

Amlodipine is a dihydropyridine calcium-channel blocker (CCB) that selectively inhibits voltage-gated L-type calcium channels in vascular smooth muscle. By preventing calcium influx, it reduces the contractile force of arterial walls, lowers peripheral vascular resistance, and decreases blood pressure without producing large chronic changes in resting heart rate. This peripheral vasodilatory action is highly relevant when studying any peptide that targets the cardiovascular system.

How Amlodipine Changes Vascular Tone and Blood-Pressure Baselines

In spontaneously hypertensive rat (SHR) models, the most widely used preclinical platform for antihypertensive research, oral doses between 1 and 10 mg/kg reduce blood pressure for at least six hours after administration. At higher maintenance doses of around 8 mg/kg per day, marked systolic blood-pressure reductions persist for 16 to 20 hours, effectively spanning an entire experimental window. This matters enormously for researchers studying peptides such as SS-31, which targets mitochondrial cardiolipin and influences cardiac energetics in pressure-overload models. If amlodipine is present in the background, observed improvements in afterload and wall stress may reflect CCB-induced resistance changes rather than peptide activity.

Key hemodynamic facts about amlodipine:

Parameter Typical Effect
Systolic BP reduction (SHR, acute) 18 to 45 mmHg
Duration per oral dose 6 to 20+ hours
Heart rate change (stable angina) Minimal chronic change
Peripheral vascular resistance Significantly reduced

The drug's long half-life, roughly 35 to 50 hours in humans, means that "overnight discontinuation" is wholly inadequate as a washout strategy. Researchers designing experiments around lab-tested peptides must plan washout periods of several days, not hours, to eliminate residual CCB influence on hemodynamic baselines.


Why Calcium-Channel Blockade Specifically Confounds Peptide Research

The confounding problem in Amlodipine and Research Peptides: How Calcium-Channel Blockade Can Confound Blood-Pressure Experiments operates through at least three distinct mechanisms, each capable of invalidating a study on its own.

Why Calcium-Channel Blockade Specifically Confounds Peptide Research

Hemodynamic Baseline Masking

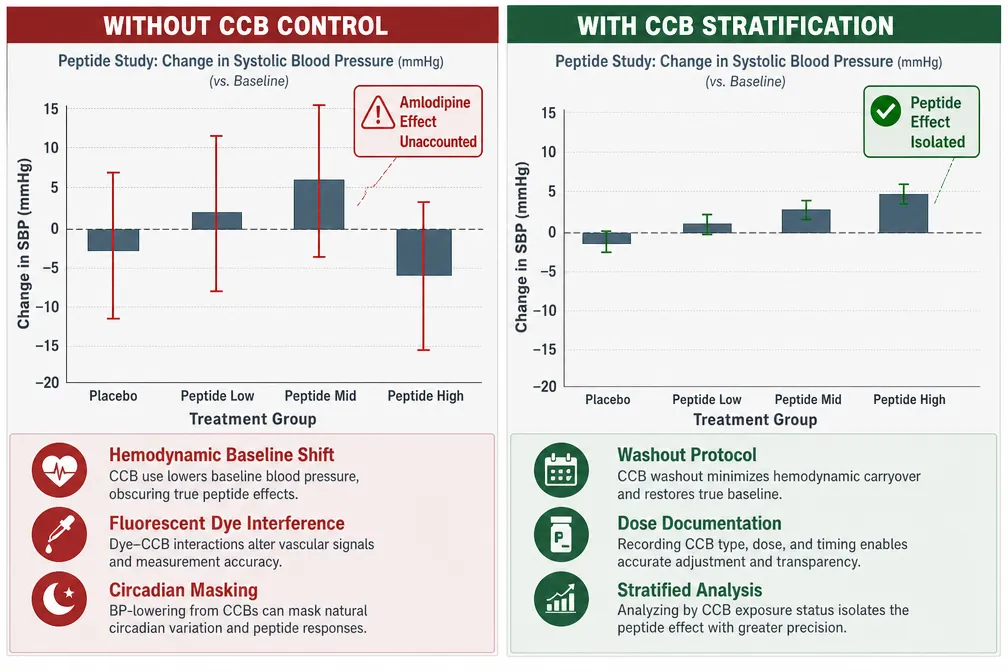
Cardioprotective peptides are typically evaluated against endpoints such as infarct size, contractility, fibrosis, and cardiomyocyte apoptosis. All of these endpoints are highly sensitive to baseline hemodynamics. A 2023 clinical analysis found that 10 mg/day of amlodipine lowered systolic blood pressure by 14.2 mmHg and diastolic blood pressure by 13.6 mmHg over eight weeks, while converting approximately 40% of patients from a "non-dipper" to a "dipper" nocturnal profile. Any concurrent peptide therapy evaluated via 24-hour ambulatory monitoring could have its chronobiologic effects masked or mimicked by these CCB-driven shifts.

For researchers studying SS-31 kidney health or cardiac remodeling, this means a peptide that genuinely reduces nocturnal blood pressure might appear no better than placebo if amlodipine has already normalized the dipper profile.

Fluorescent Calcium Imaging Interference

This is perhaps the most underappreciated confound. Amlodipine besylate accumulates in the cytoplasm and overlaps spectrally with fura-2, the most widely used fluorescent dye for measuring intracellular calcium. The drug dominates the fluorescence signal, mimicking calcium transients that do not exist. Any peptide claimed to modulate excitation-contraction coupling, including growth-hormone secretagogues or vasoactive intestinal peptides, could appear falsely effective or ineffective in fura-loaded cells exposed to amlodipine.

"Amlodipine's spectral overlap with fura-2 means that calcium imaging data collected in its presence cannot be reliably attributed to any co-administered peptide."

Confounding by Indication and Dose

Pharmacoepidemiologic research has established that both the clinical reason for prescribing a CCB and the dose level act as independent confounders. In observational peptide trials, unequal distribution of background CCB therapy across study arms, even with randomization, can systematically bias blood-pressure and remodeling outcomes. This problem is compounded by precision-dosing approaches: one trial demonstrated that app-guided amlodipine titration in 205 adults reduced mean blood pressure from 142/87 to 131/81 mmHg over 14 weeks, a moving target that would be nearly impossible to control for without explicit documentation.


Practical Design Strategies for CCB-Aware Peptide Experiments

Addressing Amlodipine and Research Peptides: How Calcium-Channel Blockade Can Confound Blood-Pressure Experiments requires deliberate protocol choices at the design stage, not post-hoc corrections.

Practical Design Strategies for CCB-Aware Peptide Experiments

Five actionable steps for researchers:

  1. Screen and document all CCB exposure, Record drug name, dose, formulation, and timing for every subject or animal before enrollment.
  2. Apply adequate washout periods, Given amlodipine's half-life, washout of at least five half-lives (seven or more days in humans) is the minimum acceptable standard.
  3. Exclude or stratify CCB-treated subjects, In studies using SS-31 mitochondrial research endpoints or similar oxidative-stress markers, exclusion is preferable; if exclusion is not feasible, stratify and adjust quantitatively.
  4. Avoid fura-based calcium imaging in amlodipine-exposed tissue, Switch to alternative calcium indicators without spectral overlap, or use CCB-naive preparations.
  5. Adjust statistical models for CCB covariates, Include CCB type, dose, and duration as covariates in regression models for blood-pressure and remodeling outcomes.

These principles apply equally to researchers working with MOTS-C peptide in metabolic-cardiovascular models, Thymosin Alpha-4 in cardiac repair studies, or VIP peptide in vascular tone experiments. Each of these compounds interacts with pathways that are directly altered by sustained calcium-channel blockade.

Checklist summary:

  • Document CCB use at baseline
  • Plan washout of at least 5 half-lives
  • Stratify groups by CCB status
  • Avoid fura-2 imaging in CCB-exposed cells
  • Report CCB covariates in all statistical models
  • Pre-register exclusion criteria related to antihypertensive therapy

Conclusion

The intersection of Amlodipine and Research Peptides: How Calcium-Channel Blockade Can Confound Blood-Pressure Experiments is a methodological blind spot with real consequences for data validity. Amlodipine's long half-life, potent hemodynamic effects, and spectral interference with calcium-imaging tools create three separate pathways through which it can distort peptide study results, masking genuine effects, generating false signals, or introducing systematic bias across study arms.

Actionable next steps for research teams in 2026:

  • Audit existing protocols for undocumented CCB exposure before data collection begins.
  • Add CCB screening as a mandatory enrollment step in any blood-pressure or calcium-signaling study.
  • Consult pharmacoepidemiology guidance on confounding by indication when designing observational peptide trials.
  • Source lab-tested peptides with verified purity certificates to eliminate compound-quality confounds alongside pharmacological ones.

Rigorous control of background antihypertensive therapy is not optional, it is the foundation on which credible peptide cardiovascular research is built.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/amlodipine-and-research-peptides-how-calcium-channel-blockade-can-confound-blood.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-04 13:05:052026-10-04 13:05:05Amlodipine and Research Peptides: How Calcium-Channel Blockade Can Confound Blood-Pressure Experiments
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top