Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: ghrh analogs

Cardiovascular Stress Markers in Growth Hormone Research: Monitoring Lisinopril and ACE Pathways Alongside Secretagogues

Cardiovascular Stress Markers in Growth Hormone Research: Monitoring Lisinopril and ACE Pathways Alongside Secretagogues

September 16, 2026/0 Comments/in Uncategorized/by

Fewer than 30% of researchers tracking growth hormone secretagogue protocols routinely measure ACE-related cardiovascular endpoints, a gap that carries real physiological consequences. As interest in GHRH analogs and synthetic secretagogues accelerates in 2026, the intersection of cardiovascular stress markers in growth hormone research and blood pressure regulation via the renin-angiotensin-aldosterone system (RAAS) has become one of the most clinically relevant monitoring challenges in the field.

When secretagogues elevate IGF-1 and promote fluid retention, the cardiovascular system absorbs much of that load. Lisinopril, an ACE inhibitor, is frequently co-administered to manage that burden, but the interaction between these two pathways demands a structured, marker-driven approach.

Key Takeaways

  • Growth hormone secretagogues raise IGF-1 and can promote sodium and fluid retention, increasing cardiac preload and blood pressure.
  • Lisinopril and other ACE inhibitors blunt RAAS activation but introduce their own monitoring needs, including potassium elevation and renal function shifts.
  • Tracking cardiovascular stress markers, hemodynamic, structural, biomarker, and vascular, is essential when combining these agents in research protocols.
  • NT-proBNP, hs-troponin, seated and ambulatory blood pressure, and echocardiographic data form the core monitoring panel.
  • Integrated monitoring of the ACE pathway alongside secretagogue use reduces the risk of undetected cardiac stress.

How Secretagogues Interact With the Cardiovascular System
How Secretagogues Interact With the Cardiovascular System

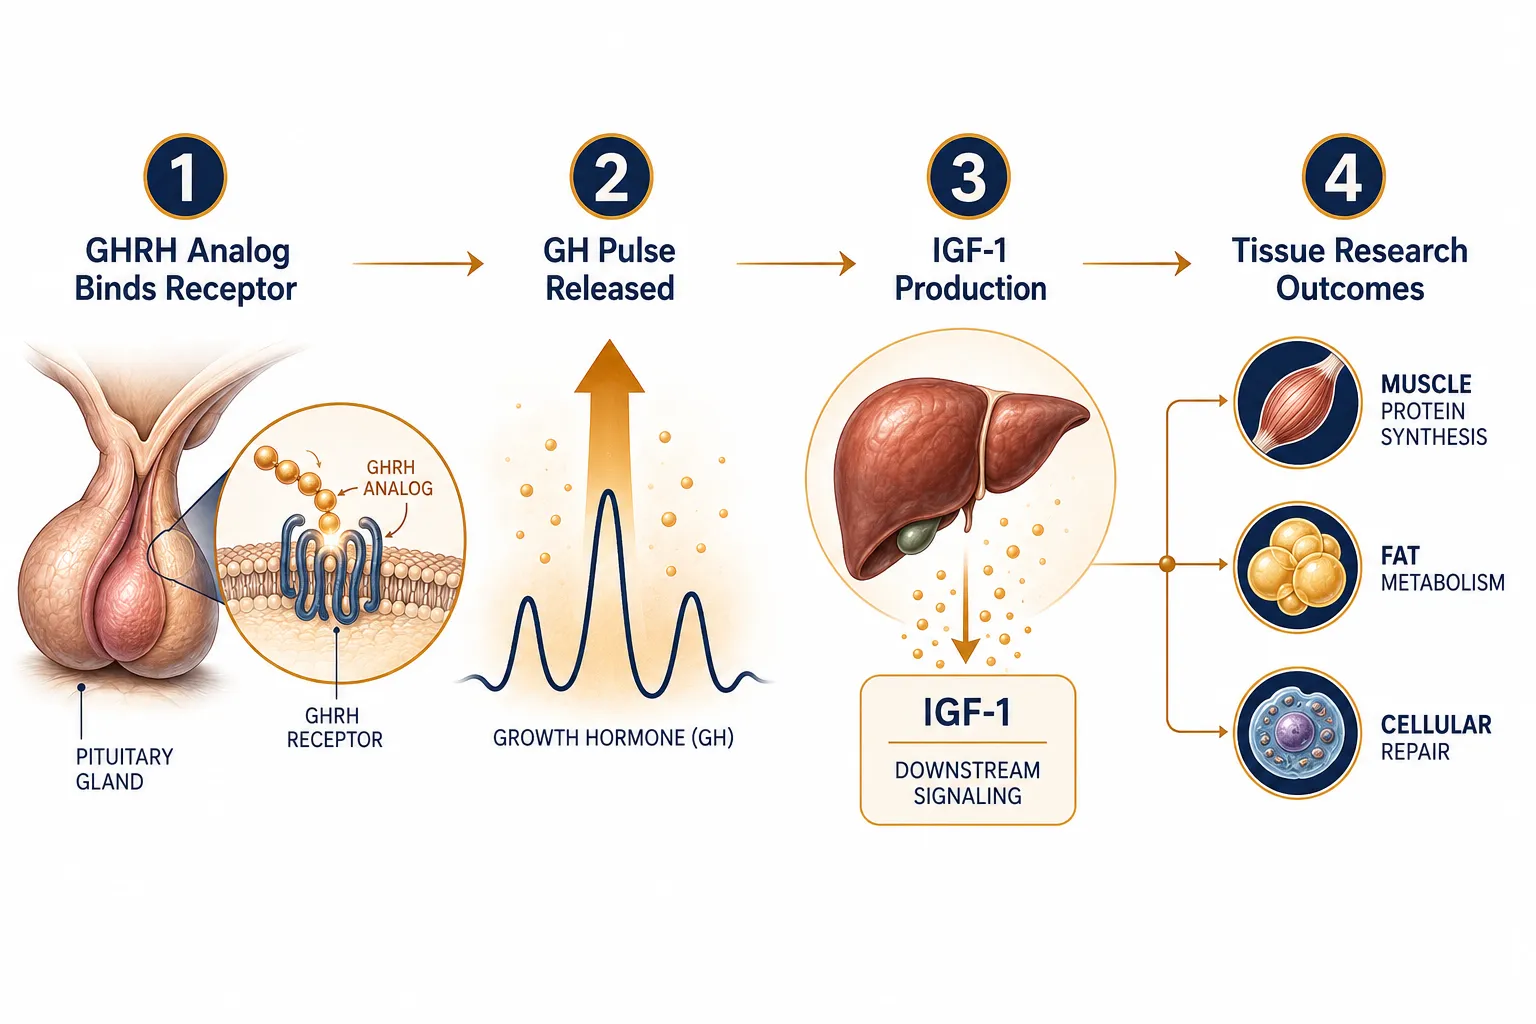
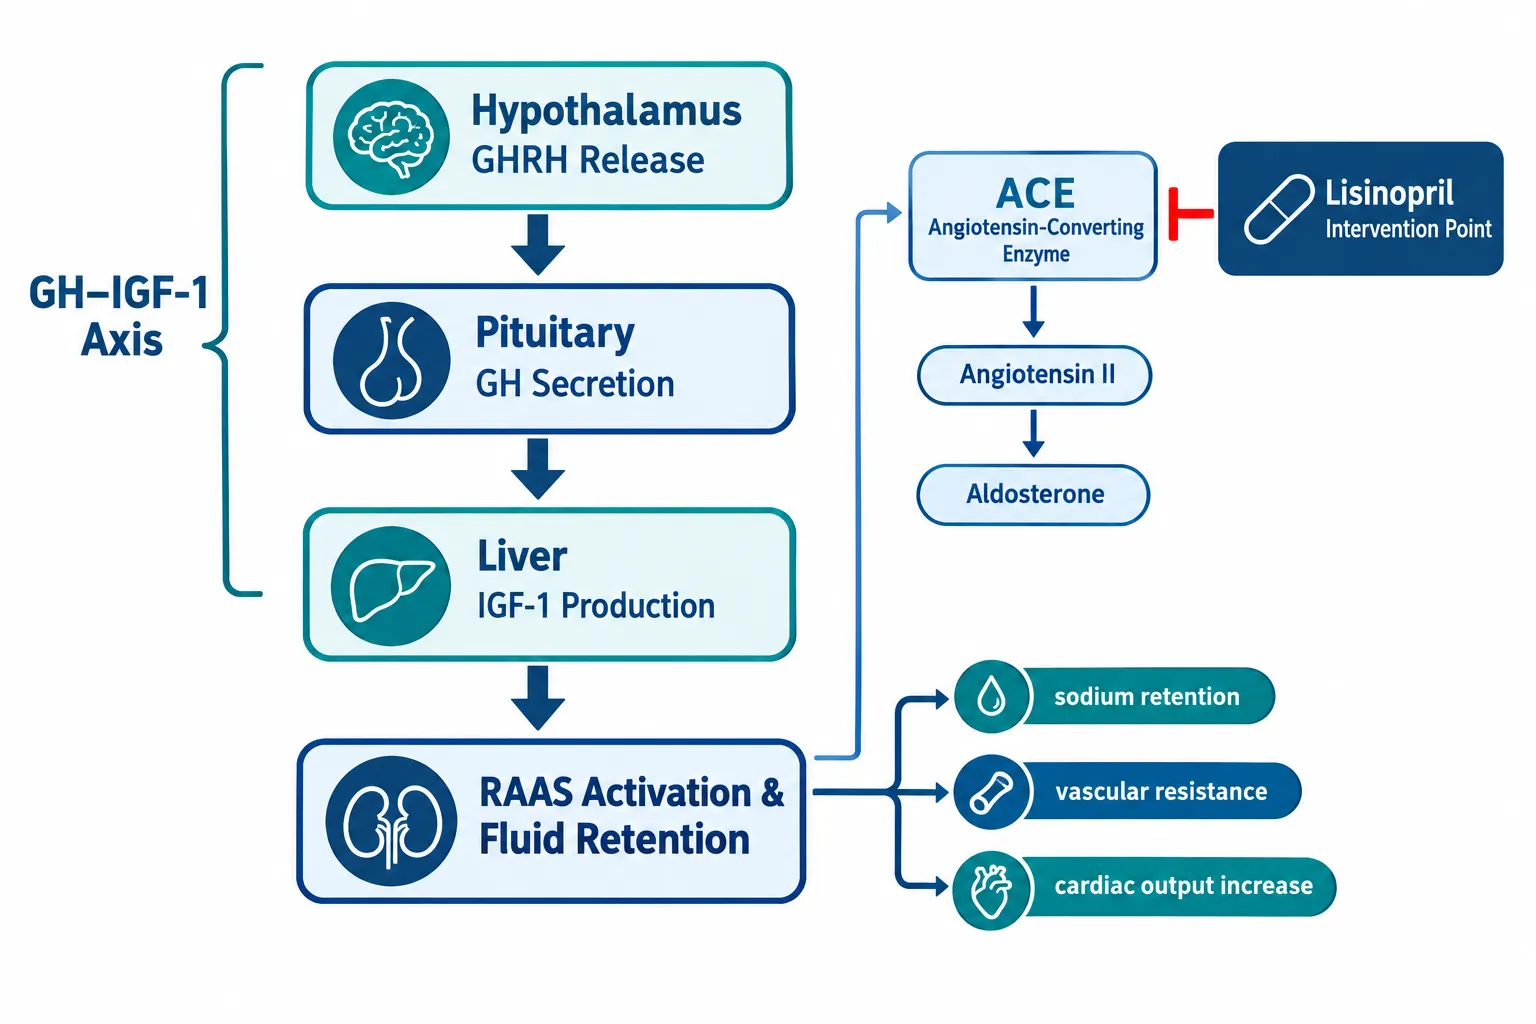
Growth hormone secretagogues, including GHRH analogs, ghrelin mimetics, and synthetic GH-releasing peptides, stimulate pituitary GH release, which in turn drives hepatic IGF-1 production. This cascade carries meaningful cardiovascular effects that researchers must account for.

IGF-1 elevation promotes myocardial growth, increases cardiac output, and enhances vascular smooth muscle responsiveness. In the short term, these effects can look beneficial. Over longer exposures, however, elevated IGF-1 contributes to left ventricular hypertrophy and arterial stiffness, both established markers of cardiovascular stress.

Ghrelin and its synthetic analogs add another layer. Research consistently shows that ghrelin-type secretagogues exert vasodilatory, anti-ischemic, and anti-apoptotic effects on cardiac tissue. They reduce peripheral vascular resistance and may lower blood pressure acutely. However, this vasodilation can interact unpredictably with ACE inhibitors, raising the risk of orthostatic hypotension.

Fluid retention is a particularly important concern. GH directly stimulates renal sodium reabsorption via the IGF-1 receptor, expanding plasma volume. This increases cardiac preload and, over time, elevates systolic blood pressure. Researchers working with IPA Sermorelin stack protocols should factor this mechanism into their baseline cardiovascular assessments.

The RAAS responds to this expanded volume by modulating aldosterone and angiotensin II levels. This is precisely where lisinopril enters the picture.

Lisinopril and ACE Pathway Dynamics in Secretagogue Protocols

Lisinopril and ACE Pathway Dynamics in Secretagogue Protocols

Lisinopril blocks ACE, the enzyme that converts angiotensin I to the potent vasoconstrictor angiotensin II. By reducing angiotensin II, lisinopril lowers peripheral resistance, reduces aldosterone-driven sodium retention, and decreases cardiac afterload. These are exactly the mechanisms that counteract GH-induced fluid retention.

"The ACE pathway and the GH/IGF-1 axis do not operate in isolation, co-administration of lisinopril alongside secretagogues creates a dynamic cardiovascular environment that requires active, structured monitoring."

However, ACE inhibition introduces its own variables. Potassium levels rise because aldosterone suppression reduces urinary potassium excretion. Renal perfusion pressure can drop, particularly in subjects with any pre-existing renal sensitivity. Bradykinin accumulates, which may amplify the vasodilatory effects already present from ghrelin-type secretagogues.

Key interaction points to monitor:

  • Blood pressure response may be exaggerated when ghrelin-type secretagogues and lisinopril are combined
  • Potassium can climb into hyperkalemic ranges without regular electrolyte testing
  • Renal function (creatinine, eGFR) may shift as RAAS suppression alters glomerular filtration dynamics
  • Fluid balance changes can mask or amplify biomarker readings

Researchers exploring peptide combinations that modulate metabolic and cardiovascular pathways, such as those reviewed in tesofensine noradrenergic and incretin-based pathway research, will recognize that multi-pathway interactions demand multi-marker monitoring frameworks.

Core Cardiovascular Stress Markers for Combined RAAS-GH Axis Monitoring
Core Cardiovascular Stress Markers for Combined RAAS-GH Axis Monitoring

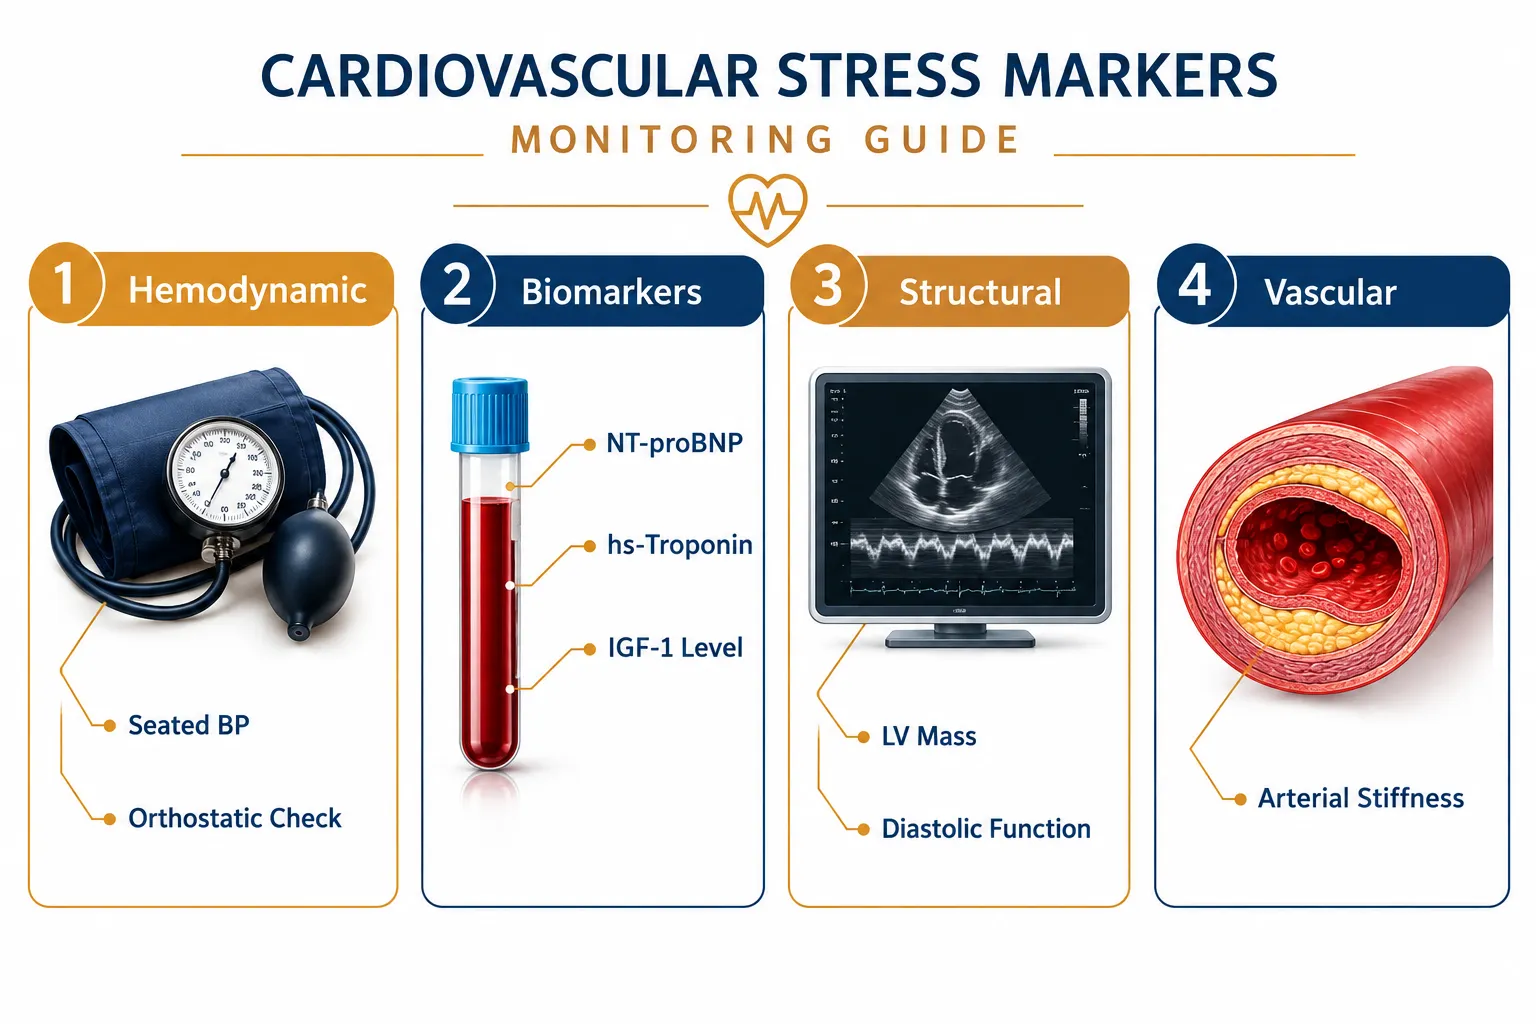
Monitoring cardiovascular stress markers in growth hormone research alongside lisinopril and ACE pathway modulation requires a structured, four-domain approach.

Hemodynamic Markers

Marker Measurement Method Key Concern
Seated blood pressure Manual or automated sphygmomanometry Hypertension from GH fluid load
Ambulatory blood pressure 24-hour ABPM device Masked hypertension patterns
Orthostatic blood pressure Supine to standing protocol Hypotension risk with ACE + ghrelin
Resting heart rate ECG or pulse oximetry Tachycardia from volume shifts

Structural Markers

Echocardiography provides the most direct window into cardiac remodeling. Left ventricular mass index, wall thickness, and both systolic and diastolic function should be assessed at baseline and at defined intervals. Diastolic dysfunction often precedes systolic changes and can appear early in GH-excess states.

Biomarker Panel

NT-proBNP is the most sensitive biomarker for detecting early cardiac wall stress and volume overload. Elevated levels signal that the heart is under pressure before symptoms appear. High-sensitivity troponin (hs-troponin) identifies subclinical myocardial injury.

Additional biomarkers include:

  • IGF-1 (to calibrate secretagogue dosing and exposure)
  • Serum creatinine and eGFR (renal safety on ACE inhibitor)
  • Potassium and sodium (electrolyte balance under RAAS suppression)
  • Fasting glucose and lipid panel (metabolic context)

Research on mitochondrial cardioprotection compounds such as those examined in SS-31 mitochondrial research highlights how cellular stress markers can complement systemic biomarker panels in cardiovascular monitoring.

Vascular Markers

Arterial stiffness indices, measured via pulse wave velocity or augmentation index, capture changes in large-vessel compliance that echocardiography and biomarkers may miss. Endothelial function assessment adds further resolution in longer-duration protocols.

Practical Monitoring Frequency and Protocol Design

Effective cardiovascular stress monitoring in growth hormone research is not a one-time assessment. A tiered frequency model works best:

Baseline (before protocol initiation): Full panel, hemodynamic, echocardiographic, biomarker, and vascular measures.

Early phase (weeks 2-4): Blood pressure, heart rate, potassium, creatinine, and eGFR. This window captures the most acute RAAS-GH interaction effects.

Mid-protocol (weeks 6-12): Repeat biomarker panel including NT-proBNP and hs-troponin. Reassess IGF-1 to confirm secretagogue response is within target range.

End of protocol: Full repeat of baseline panel plus echocardiographic comparison for structural changes.

Researchers working with GLP-based peptide compounds, including those available as GLP-3 Reta 10mg or GLP-3 Reta 20mg, should apply similarly structured cardiovascular monitoring, as GLP receptor pathways also influence cardiac output and vascular tone.

Conclusion

Cardiovascular stress markers in growth hormone research represent a non-negotiable component of responsible secretagogue protocol design, particularly when lisinopril and ACE pathway modulation are part of the picture. The interaction between GH-driven fluid retention, IGF-1-mediated cardiac remodeling, and ACE inhibitor-induced RAAS suppression creates a layered hemodynamic environment that no single marker can fully capture.

Actionable next steps for researchers:

  1. Establish a full cardiovascular baseline before initiating any secretagogue-lisinopril combination protocol.
  2. Prioritize NT-proBNP, hs-troponin, potassium, and eGFR as the minimum biomarker panel throughout the study period.
  3. Use ambulatory blood pressure monitoring to detect masked hypertension or exaggerated hypotensive responses.
  4. Schedule echocardiographic assessment at baseline and protocol end to quantify structural changes.
  5. Adjust secretagogue dosing based on IGF-1 levels and correlate with hemodynamic trends rather than treating them as independent variables.

Structured monitoring transforms cardiovascular risk from an unknown variable into a manageable, measurable research parameter.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cardiovascular-stress-markers-in-growth-hormone-research-monitoring-lisinopril-a.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-16 13:07:362026-09-16 13:07:36Cardiovascular Stress Markers in Growth Hormone Research: Monitoring Lisinopril and ACE Pathways Alongside Secretagogues
CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show

September 2, 2026/0 Comments/in Uncategorized/by

Growth hormone secretagogue research has quietly shifted gears. Where earlier studies focused almost exclusively on peak GH output, the conversation around CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show has expanded to include tissue recovery timelines, glucose-handling endpoints, and combination stacking strategies that were barely discussed five years ago. Researchers and clinicians in 2026 are asking more nuanced questions, not just "does IGF-1 rise?" but "what does that rise actually do in a metabolic or recovery context?"

Key Takeaways

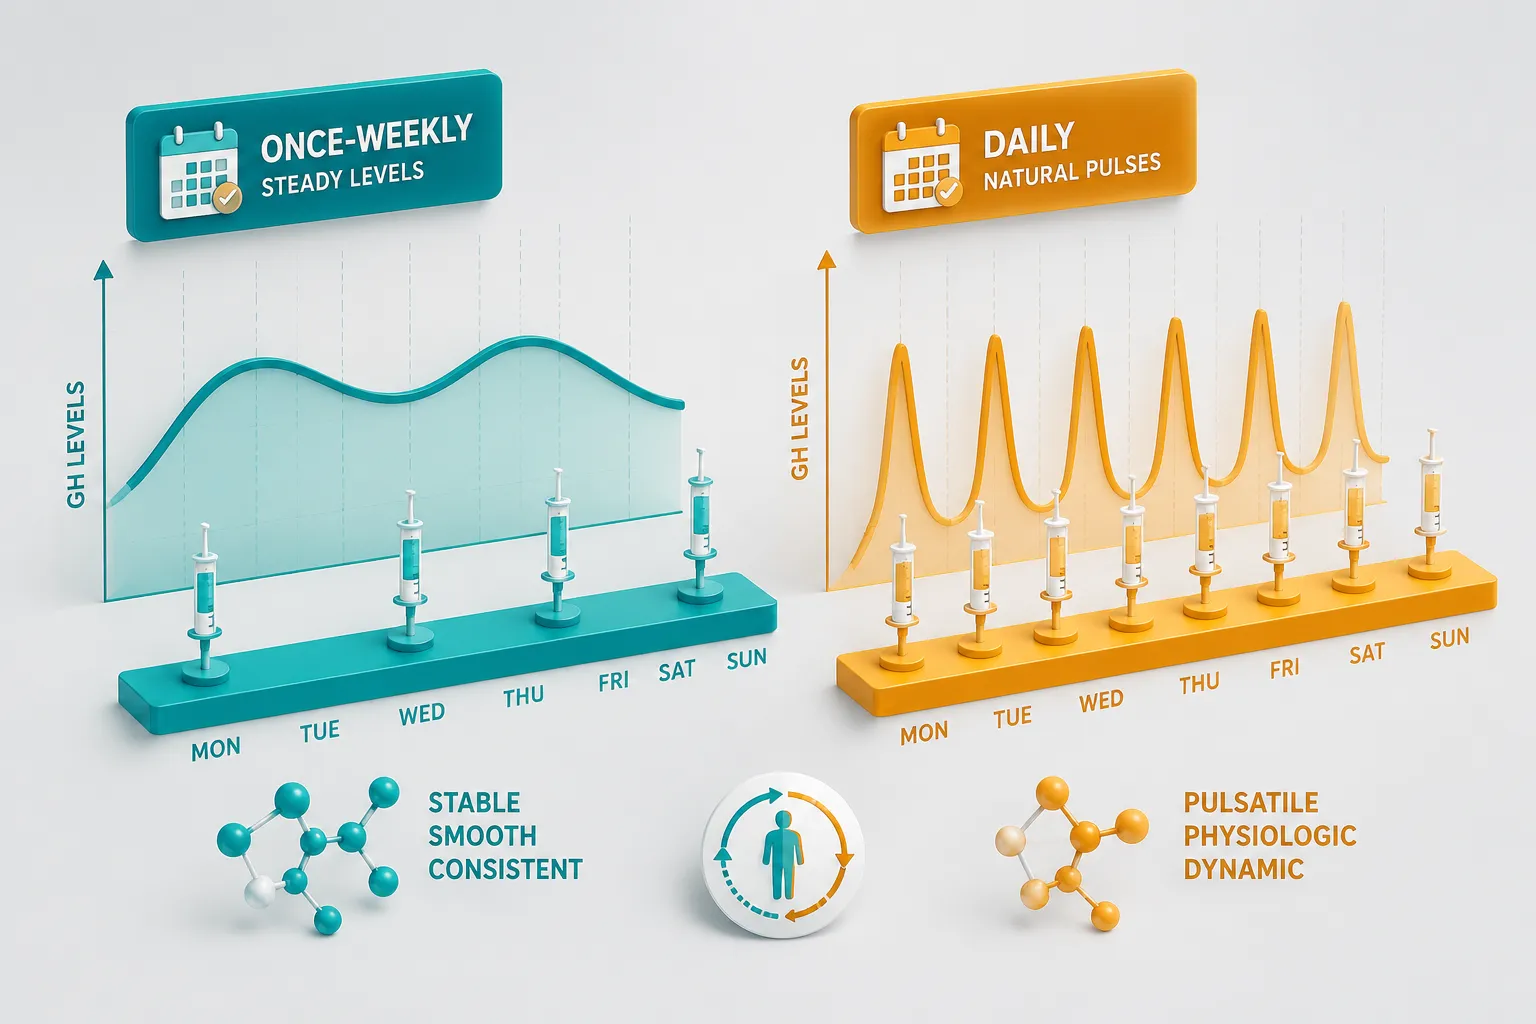
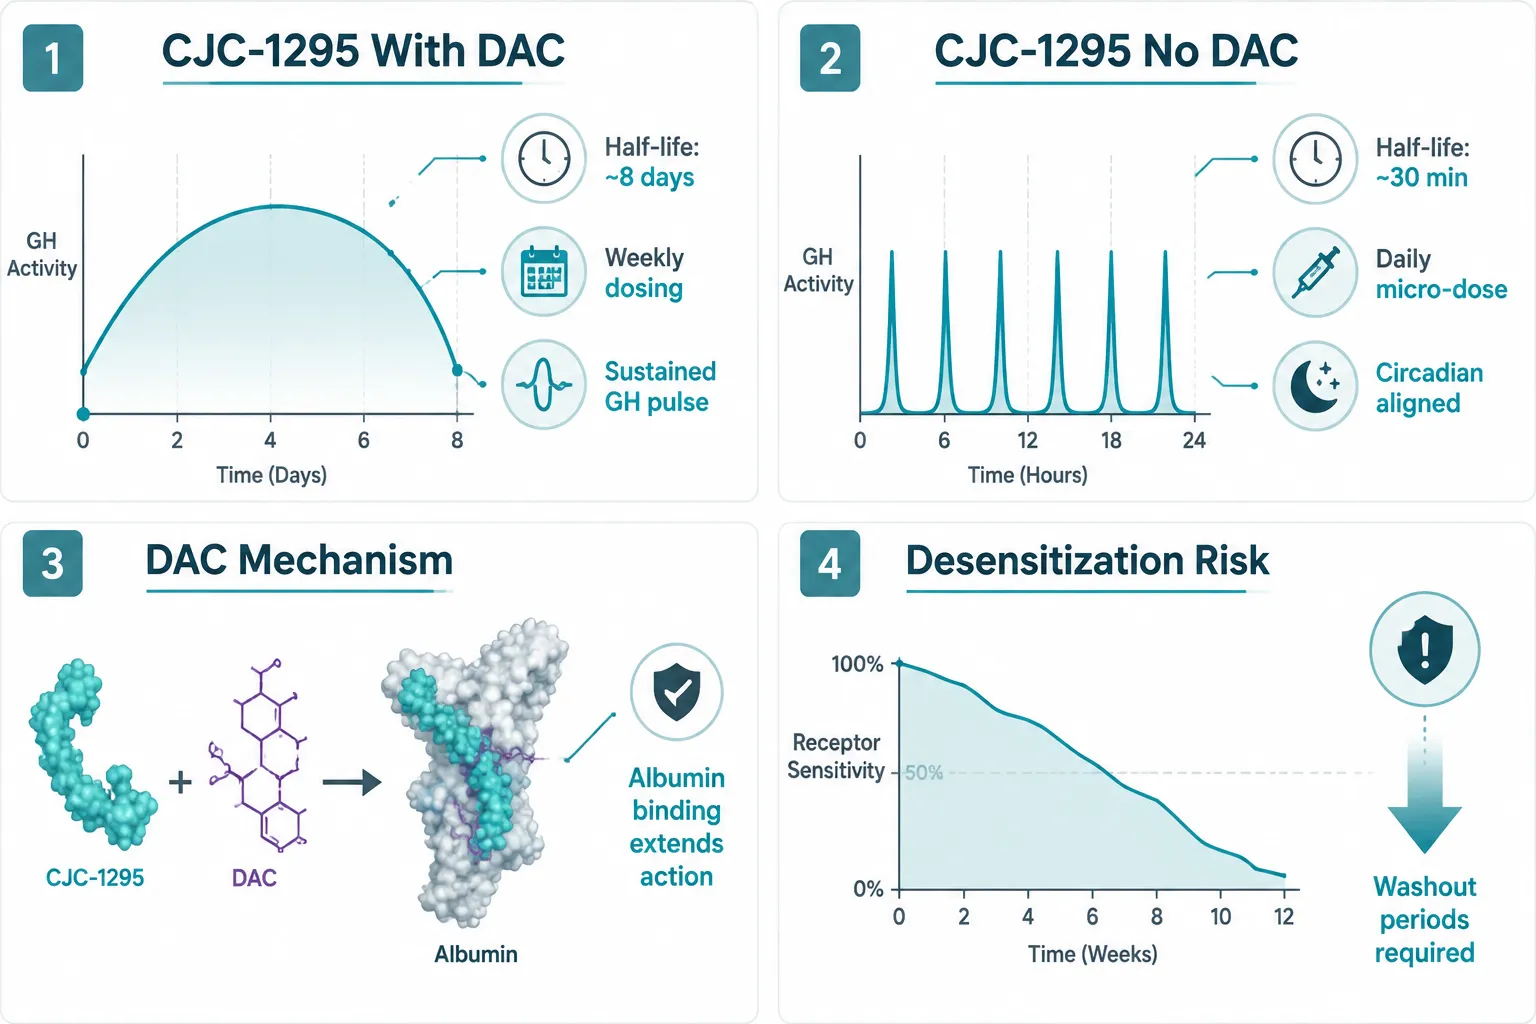
  • CJC‑1295 with DAC offers a prolonged half-life suited to weekly dosing, while the no-DAC form aligns better with circadian-timed, daily micro-dose protocols.
  • Stacking CJC‑1295 with ipamorelin has become the dominant 2026 protocol pattern in both clinical and research settings.
  • IGF-1 elevation is well-documented, but hard endpoints for recovery and body composition remain limited in the published evidence base.
  • Desensitization risk with the DAC form makes structured washout periods a standard protocol feature in 2026 monographs.
  • Combination protocols now extend to Tesamorelin and metabolic peptides, broadening the research scope beyond classic GH modeling.

Understanding the Two Forms: DAC vs. No-DAC

Understanding the Two Forms: DAC vs. No-DAC

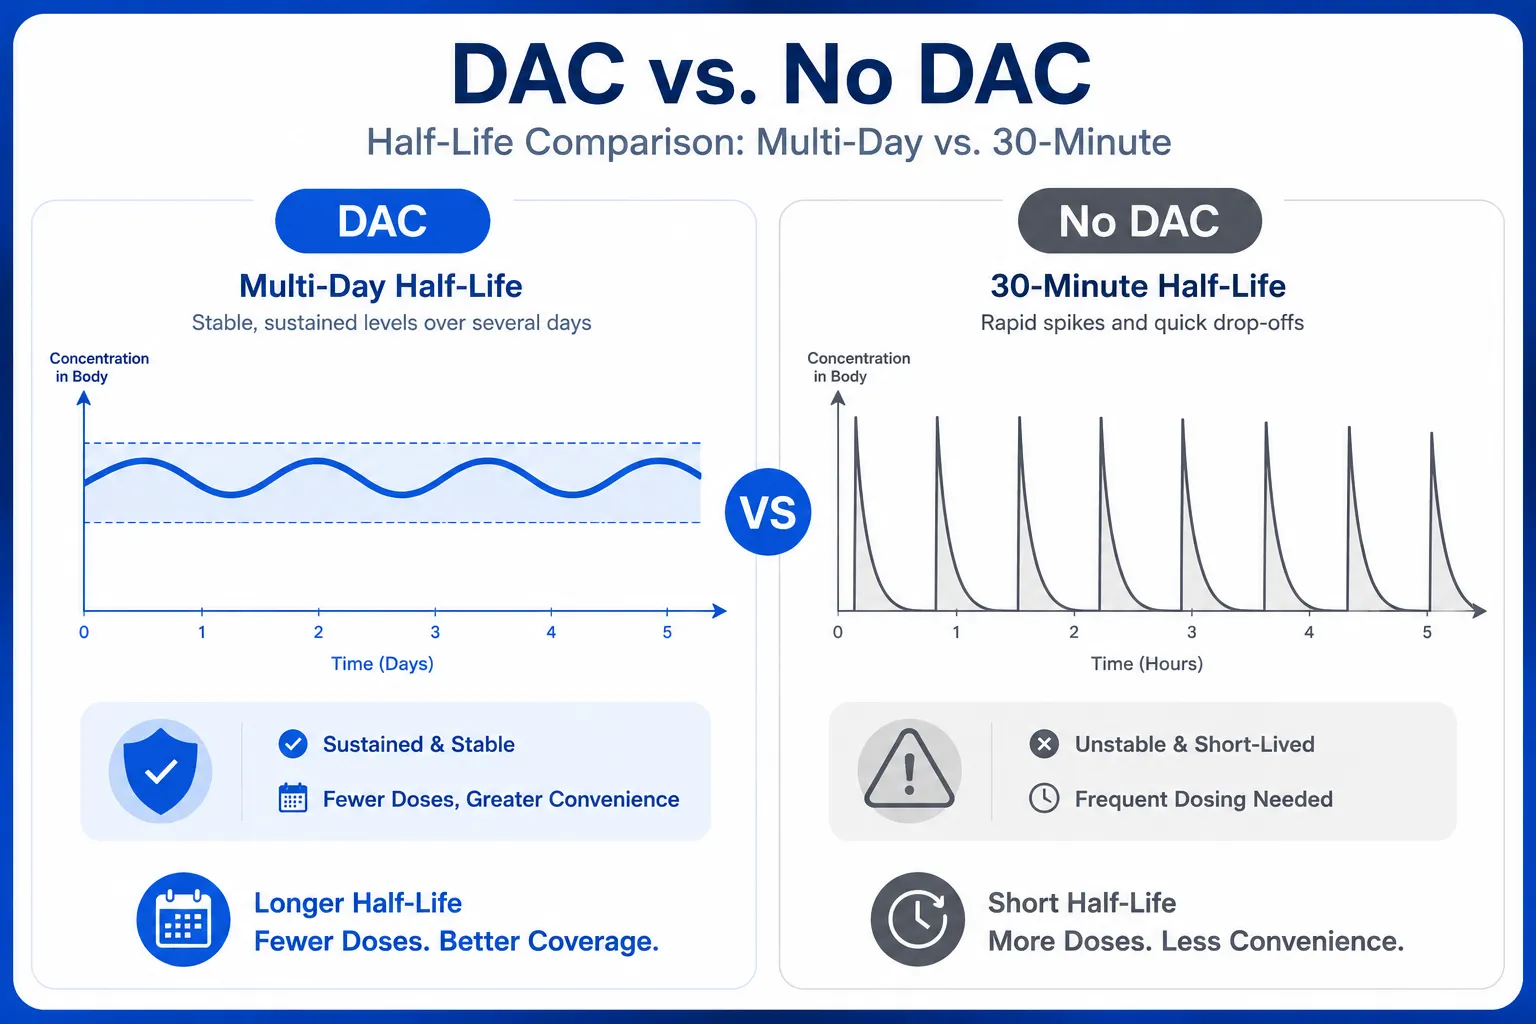
The core structural difference between the two variants drives nearly every protocol decision. CJC‑1295 with DAC (Drug Affinity Complex) binds to albumin in the bloodstream, dramatically extending its half-life to approximately eight days. This makes once-weekly or twice-monthly dosing pharmacologically feasible and reduces injection burden in longer research cycles.

CJC‑1295 without DAC, sometimes called Modified GRF(1-29), has a half-life of roughly 30 minutes. That short window is not a disadvantage in every context. Researchers exploring circadian-aligned dosing argue that brief, timed pulses more closely mimic the body's natural growth hormone release patterns, particularly when administered before sleep or around training windows.

Key pharmacokinetic comparison:

Feature With DAC Without DAC
Half-life ~8 days ~30 minutes
Dosing frequency Weekly or bi-weekly Daily or twice daily
GH pulse pattern Sustained elevation Acute, pulsatile
Desensitization risk Higher Lower
Protocol washout need Yes, structured Minimal

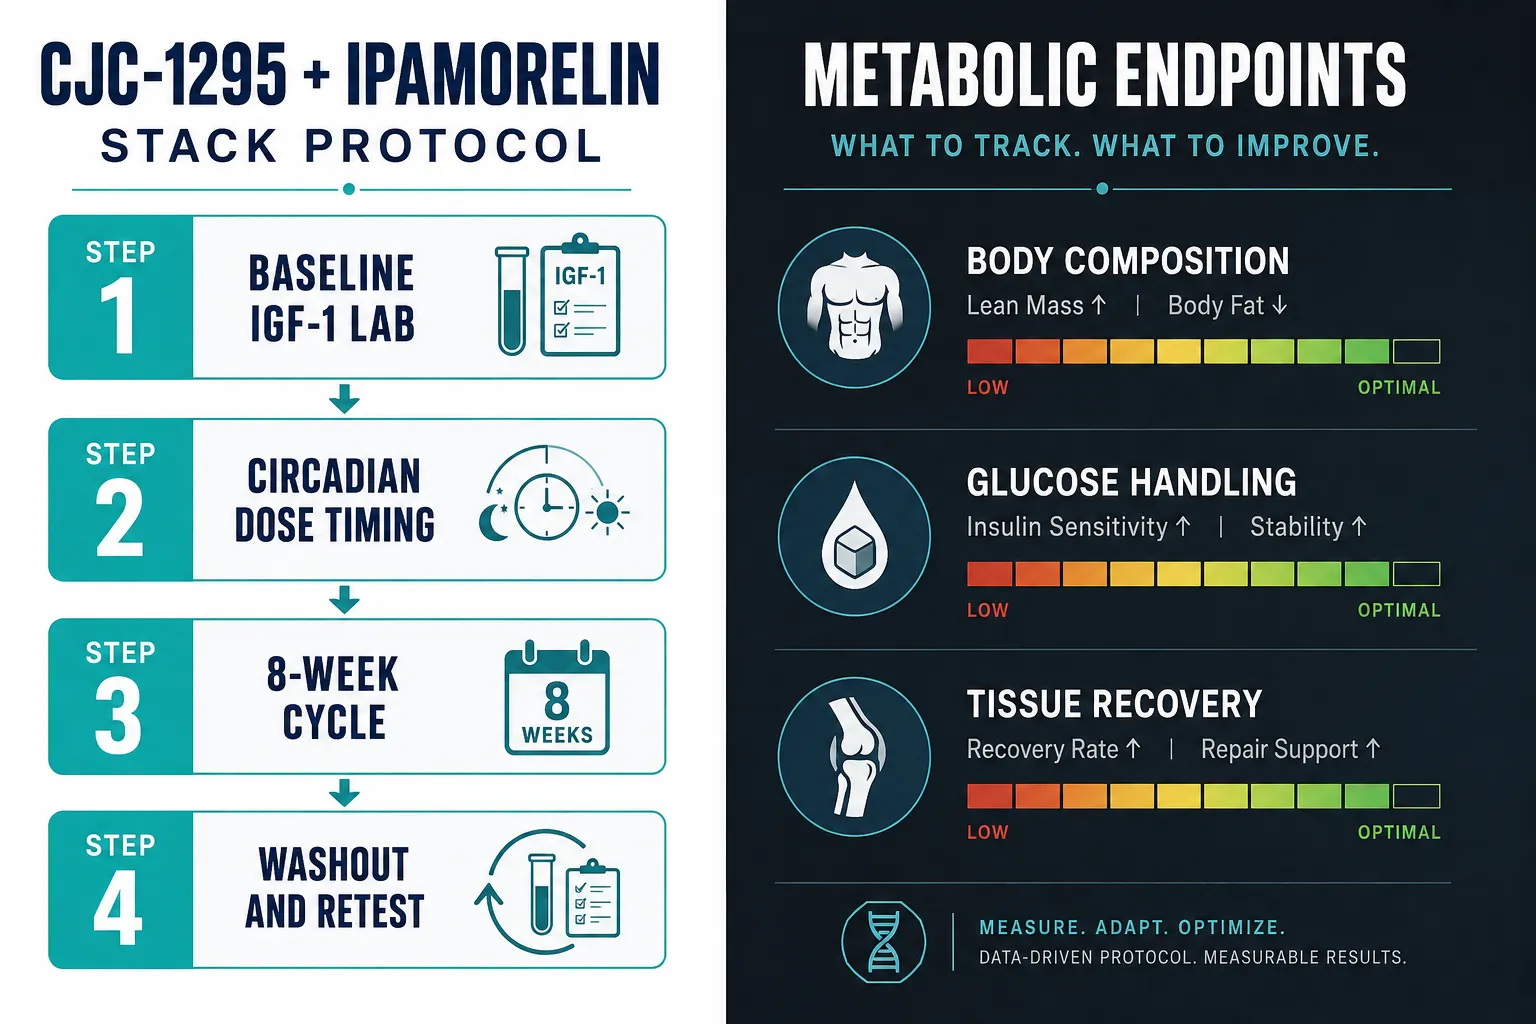
Desensitization is a genuine concern with the DAC form. Prolonged receptor stimulation can blunt pituitary responsiveness over time. Current somatotropin research protocols in 2026 address this by building in four-to-six-week washout periods after eight-to-twelve-week active cycles.

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show About Combination Stacking

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show About Com

The most significant protocol shift in 2026 is the near-universal pairing of CJC‑1295 with ipamorelin. Ipamorelin is a selective ghrelin receptor agonist that stimulates GH release through a complementary pathway. Together, the two peptides produce a synergistic GH pulse without the cortisol or prolactin elevation associated with older secretagogues.

"The combination of a GHRH analog with a selective ghrelin mimetic has become the reference stack in 2026 protocol literature, it amplifies the GH signal while keeping the hormonal side-effect profile narrow."

For researchers interested in this pairing, resources on sermorelin, ipamorelin, and CJC-1295 dosing provide useful context on how dosing ratios are being structured. A related product reference for lab-grade material is the CJC-1295 IPA 10mg formulation used in current research settings.

Beyond ipamorelin, 2026 protocols are increasingly incorporating Tesamorelin, an FDA-approved GHRH analog with a documented record from HIV lipodystrophy trials. That clinical history provides safety signals that pure research peptides lack. Researchers exploring this avenue can review the Tesamorelin and CJC-1295 combination framework, which positions both analogs within the broader GHRH class. Multi-peptide blends, such as those covered in Tesamorelin, CJC-1295, and ipamorelin 12mg blend protocols, are also appearing in emerging metabolic research designs.

Common 2026 stacking configurations:

  • CJC‑1295 (no DAC) + ipamorelin: nightly, circadian-timed
  • CJC‑1295 (with DAC) + ipamorelin: weekly CJC, daily ipamorelin
  • CJC‑1295 + Tesamorelin + ipamorelin: multi-target metabolic protocols
  • CJC‑1295 + AOD-9604 blends: body composition-focused research designs

What the Evidence Actually Shows, and Where It Falls Short

What the Evidence Actually Shows, and Where It Falls Short

Honest assessment of the evidence base matters here. IGF-1 elevation following CJC‑1295 administration is consistently documented across multiple study designs. That finding is robust. What remains less clear is the translation of that IGF-1 rise into hard clinical endpoints.

What is reasonably supported:

  • Dose-dependent increases in IGF-1 and GH
  • Improved lean mass markers in some body composition studies
  • Potential benefits in tissue recovery research contexts, particularly around collagen synthesis pathways
  • Modest improvements in sleep quality linked to nocturnal GH pulsatility

What remains speculative or under-studied:

  • Long-term glucose metabolism effects at fixed clinic doses vs. weight-based trial doses
  • Durability of body composition changes after cycle cessation
  • Comparative efficacy of DAC vs. no-DAC forms on recovery-specific endpoints
  • Safety profile in populations beyond healthy adults and HIV lipodystrophy patients

The gap between weight-based dosing used in clinical trials and the fixed doses common in clinic or biohacking settings is a persistent methodological problem. Most trial data comes from weight-adjusted protocols; most real-world use does not follow that model. Researchers tracking tissue repair research outcomes need to account for this discrepancy when interpreting results.

Lab-based monitoring, specifically IGF-1, fasting glucose, and HbA1c panels, is now considered standard practice in responsible 2026 protocol designs, particularly for cycles exceeding eight weeks.

Conclusion

CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show points toward a maturing field that is moving beyond simple GH elevation as a goal. The DAC form suits sustained, low-frequency dosing with structured washout; the no-DAC form fits circadian-aligned, pulsatile strategies. Combination stacking with ipamorelin and Tesamorelin is now the research norm rather than the exception.

Actionable next steps for researchers and clinicians:

  1. Select the CJC‑1295 variant based on dosing frequency needs and desensitization tolerance, not convenience alone.
  2. Pair with ipamorelin for synergistic GH pulse amplification with a cleaner hormonal side-effect profile.
  3. Establish baseline IGF-1, fasting glucose, and HbA1c before any cycle begins.
  4. Build washout periods into DAC-based protocols, typically four to six weeks after an eight-to-twelve-week active phase.
  5. Interpret body composition and recovery outcomes against trial-dosing literature with appropriate caution given the fixed-dose gap.

The evidence base will sharpen as more combination protocols generate structured outcome data. Until then, disciplined lab monitoring and conservative cycle design remain the most defensible approach.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cjc-1295-with-and-without-dac-in-emerging-recovery-and-metabolic-research-what-2-1.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-02 13:04:042026-09-02 13:04:04CJC‑1295 With and Without DAC in Emerging Recovery and Metabolic Research: What 2026 Protocols Are Starting to Show
Peptides in Basic Cell Biology: How GLP, GHRH, and Mitochondrial Peptides Are Used to Probe Cellular Signaling Pathways

Peptides in Basic Cell Biology: How GLP, GHRH, and Mitochondrial Peptides Are Used to Probe Cellular Signaling Pathways

August 25, 2026/0 Comments/in Uncategorized/by

Fewer than two decades ago, researchers had limited molecular tools to dissect the difference between a receptor's metabolic function and its stress-response behavior. Today, peptides in basic cell biology, specifically how GLP, GHRH, and mitochondrial peptides are used to probe cellular signaling pathways, have become one of the most productive strategies in preclinical research. These molecules are not just therapeutic candidates; they are precision instruments for interrogating how cells sense, respond, and adapt at the molecular level.

Key Takeaways

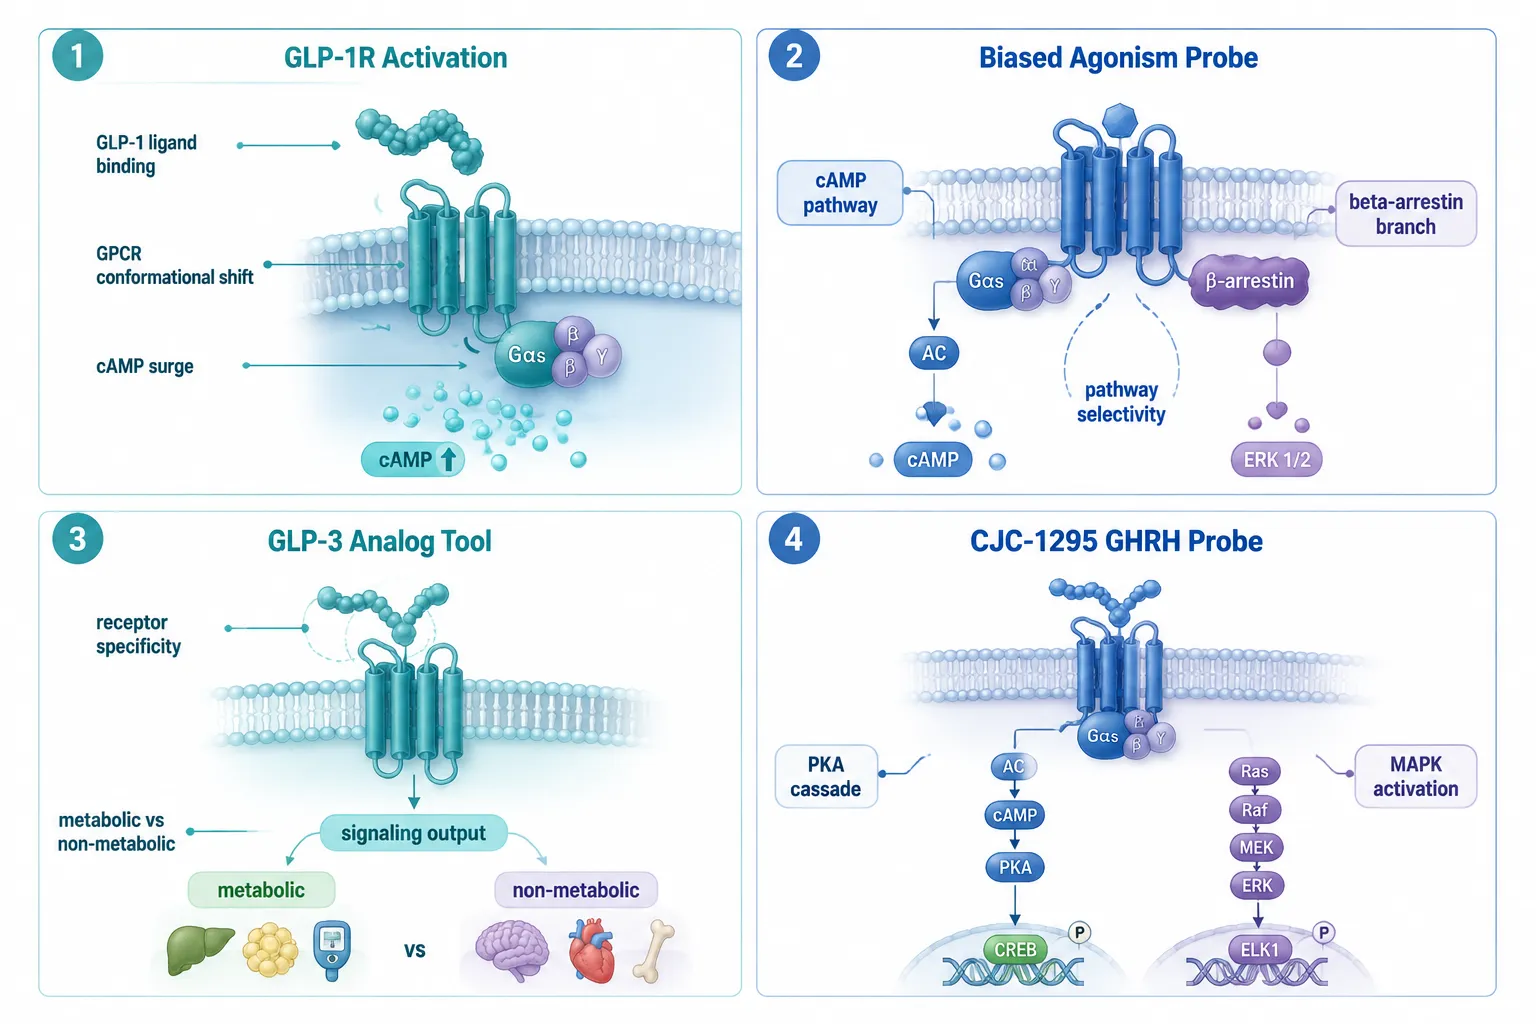
  • GLP-1 analogs and GLP-3 compounds serve as selective probes for separating cAMP-driven metabolic signaling from beta-arrestin-mediated stress responses in cultured cells.
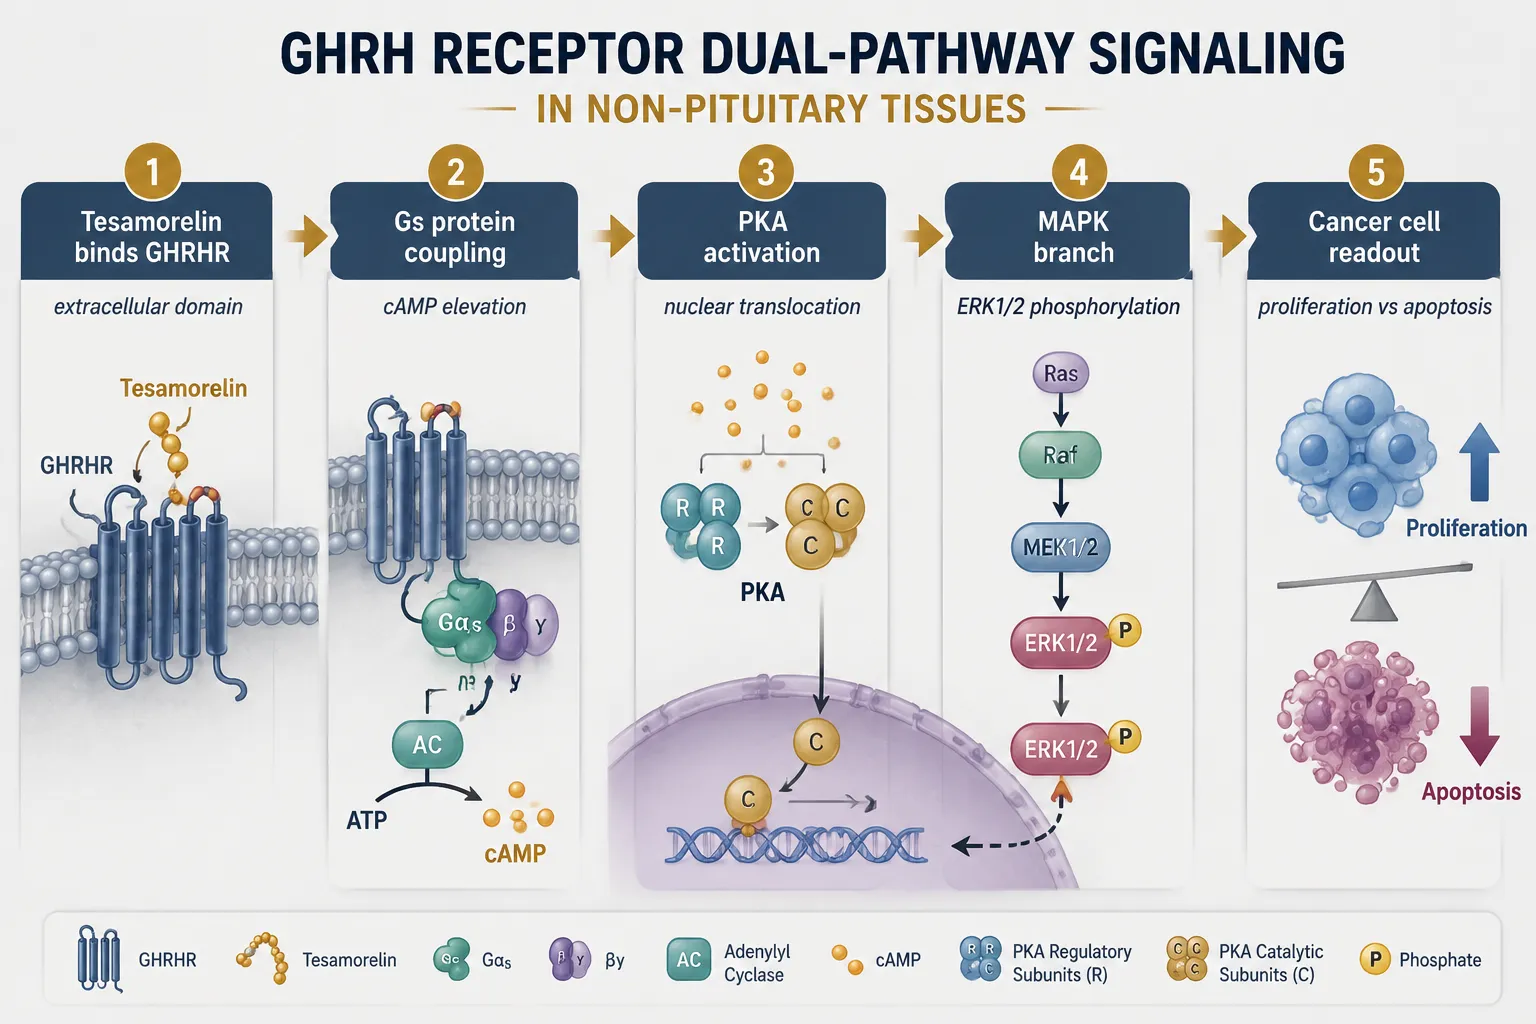
  • GHRH analogs, including tesa and CJC-1295, activate dual intracellular pathways in non-pituitary tissues, making them valuable tools for cancer and metabolic signaling research.
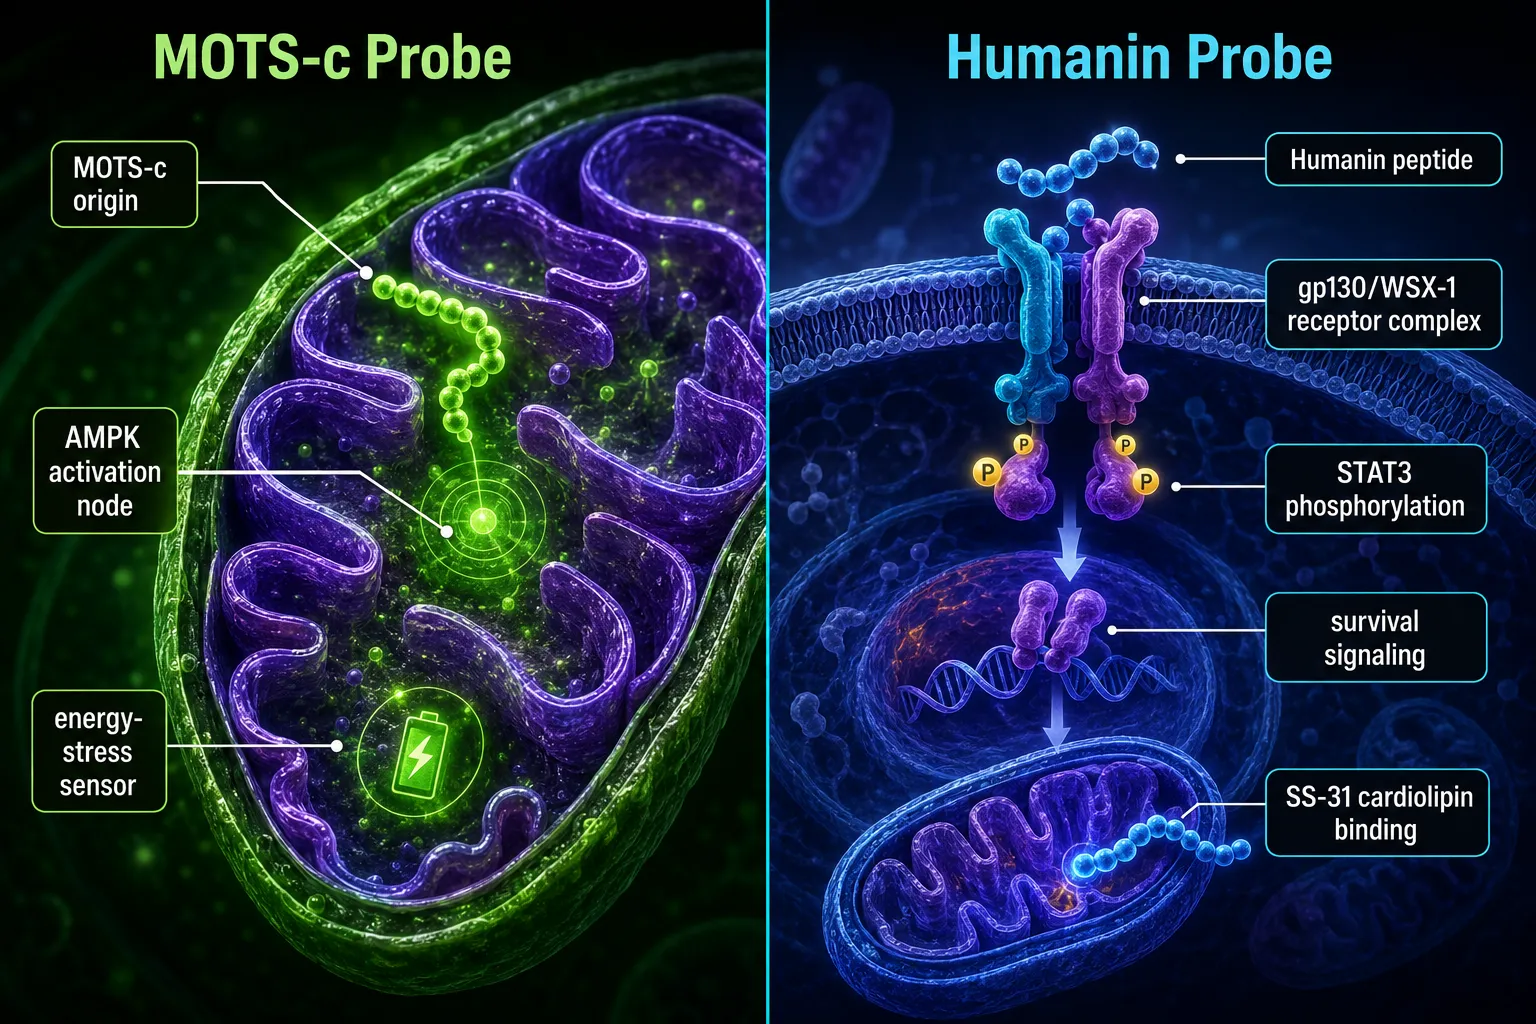
  • Mitochondrial peptides, MOTS-c, Humanin, and SS-31, target distinct organelle-level signaling nodes, including AMPK, STAT3, and cardiolipin-associated pathways.
  • Biased agonism at GPCRs can now be mapped using peptide probes designed to favor one downstream branch over another.
  • Research-grade purity and verified composition are essential when using these peptides as signaling tools in cell-based assays.

GLP Peptides as Probes of Receptor-Level Signaling Architecture

GLP Peptides as Probes of Receptor-Level Signaling Architecture

The glucagon-like peptide family has moved well beyond its association with insulin secretion. In 2026, the structural pharmacology of the GLP-1 receptor (GLP-1R) has been mapped in enough detail that researchers can now design experiments that selectively activate one downstream branch while suppressing another, a technique called biased agonism.

When GLP-1 analogs bind GLP-1R, two major intracellular cascades compete for activation:

  • cAMP/PKA pathway, classically linked to insulin secretion and metabolic regulation
  • Beta-arrestin pathway, associated with receptor internalization, ER stress responses, and apoptosis signaling

By using structurally distinct GLP-1 analogs, cell biologists can isolate which pathway drives a given phenotype. GLP-3 analogs extend this toolkit further, offering receptor-selectivity profiles that differ from GLP-1, allowing researchers to probe metabolic versus non-metabolic signaling in the same cell line without cross-activation. For researchers sourcing these tools, GLP-1 peptides must meet strict purity standards to produce reproducible assay results.

A comprehensive overview of how these molecules interact at the receptor and cellular level is available in the guide to peptide mechanisms from GLP-3 and retatrutide to CJC-1295 and MOTS-c, which outlines the mechanistic distinctions between family members.

GLP-1R as a stress-pathway sensor has also gained attention. Updated research in 2026 confirms that GLP-1R agonists can modulate ER stress markers and apoptosis regulators in pancreatic beta cells and neuronal cultures, independent of their glucose-lowering effects. This makes them dual-purpose probes: metabolic readouts and stress-biology readouts from the same receptor system.

"The ability to separate cAMP signaling from beta-arrestin recruitment at GLP-1R has transformed it from a therapeutic target into a precision cell biology instrument."

For a detailed breakdown of GLP-1, GLP-2, and GLP-3 distinctions, the researcher's guide to the GLP peptide family provides structured comparisons of receptor binding and downstream effects.

GHRH Analogs: Dual-Pathway GPCR Probes in Non-Pituitary Tissues

GHRH Analogs: Dual-Pathway GPCR Probes in Non-Pituitary Tissues

Growth hormone-releasing hormone (GHRH) and its receptor (GHRHR) were once studied almost exclusively in pituitary biology. Research from 2025 through 2026 has firmly established GHRHR as a dual-pathway GPCR expressed in multiple non-pituitary tissues, including lung, breast, prostate, and cardiac cells.

This broader expression profile makes GHRH analogs, particularly tesa and CJC-1295, highly useful as cell biology probes. When applied to cultured non-pituitary cells, these analogs activate:

Pathway Key Effectors Research Application
Gs/cAMP/PKA CREB, gene transcription Metabolic and proliferative signaling
MAPK/ERK1/2 Cell cycle regulators Cancer signaling, apoptosis resistance

The ability to selectively engage one arm over the other, depending on analog structure, concentration, and cell type, gives researchers a controllable system for studying how GPCR signaling bifurcates inside the cell.

In cancer cell lines, GHRH analogs have been used to probe the balance between pro-survival and pro-apoptotic outputs from the same receptor. This has practical value for understanding how tumor cells co-opt hormonal signaling for growth. CJC-1295, a long-acting GHRH analog, is particularly useful in extended time-course experiments where sustained receptor occupancy is needed to observe downstream transcriptional changes.

Mitochondrial Peptides: MOTS-c, Humanin, and SS-31 as Organelle-Level Signaling Tools

Mitochondrial Peptides: MOTS-c, Humanin, and SS-31 as Organelle-Level Signaling Tools

The discovery that mitochondria encode their own bioactive peptides has opened an entirely new dimension in the study of peptides in basic cell biology: how GLP, GHRH, and mitochondrial peptides are used to probe cellular signaling pathways. Three peptides have emerged as primary research tools: MOTS-c, Humanin, and SS-31.

MOTS-c and AMPK-Centered Energy Stress Signaling

MOTS-c is encoded within the mitochondrial 12S rRNA gene and functions as a retrograde signal, moving from mitochondria to the nucleus in response to metabolic stress. In cell culture models, MOTS-c activates AMPK, the master energy sensor, and modulates folate and methionine metabolism. As of July 2026, MOTS-c is used to probe how cells detect and respond to nutrient deprivation and oxidative stress, making it a valuable tool for metabolic disease research.

Humanin and the gp130/STAT3 Survival Axis

Humanin activates a receptor complex involving gp130 and WSX-1, triggering STAT3 phosphorylation and downstream survival gene expression. Researchers use Humanin to map the boundary between cellular survival and apoptosis, particularly in neuronal and cardiac cell models. Its selectivity for this pathway makes it a clean probe for STAT3-dependent transcription without the off-target effects of cytokine stimulation.

SS-31: Cardiolipin Binding and Membrane Dynamics

SS-31 targets cardiolipin, a phospholipid unique to the inner mitochondrial membrane. By stabilizing cardiolipin-cytochrome c interactions, SS-31 helps researchers study how mitochondrial membrane integrity influences electron transport chain efficiency and reactive oxygen species (ROS) production. Detailed research applications are covered in the SS-31 mitochondrial dynamics resource and in SS-31 10mg research peptide considerations.

For researchers sourcing these tools, verified composition is non-negotiable. Lab tested peptides with documented certificates of analysis ensure that assay results reflect biology, not contaminant artifacts.

Conclusion

The use of peptides in basic cell biology, specifically how GLP, GHRH, and mitochondrial peptides are used to probe cellular signaling pathways, represents one of the most versatile and rapidly evolving areas of preclinical research in 2026. Each peptide class offers a distinct entry point into cell signaling: GLP analogs dissect GPCR bias at the receptor level, GHRH analogs map dual-pathway activation across tissue types, and mitochondrial peptides illuminate organelle-to-nucleus communication.

Actionable next steps for researchers:

  1. Define the specific signaling node of interest before selecting a peptide probe, pathway selectivity is the primary selection criterion.
  2. Use structurally characterized analogs (tesa, CJC-1295, MOTS-c) with documented receptor binding profiles to ensure experimental specificity.
  3. Source only pure, tested peptides with third-party verified purity to maintain assay integrity.
  4. Cross-validate findings using at least two peptide probes targeting the same pathway node to rule out off-target effects.
  5. Consult current structural pharmacology data when designing biased agonism experiments at GLP-1R or GHRHR.

As mitochondrial peptide biology and GPCR structural pharmacology continue to converge, the toolkit available for dissecting cellular signaling will only grow more precise.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/peptides-in-basic-cell-biology-how-glp-ghrh-and-mitochondrial-peptides-are-used.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-25 13:05:312026-08-25 13:05:31Peptides in Basic Cell Biology: How GLP, GHRH, and Mitochondrial Peptides Are Used to Probe Cellular Signaling Pathways
Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides

Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides

August 18, 2026/0 Comments/in Uncategorized/by

Over 100 distinct peptide-based drugs are currently in active clinical development worldwide, yet most researchers encounter these molecules without a clear structural map of how they relate to one another. This guide on Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides addresses that gap directly, building a scientific foundation before diving into specific compound families.

Key Takeaways

  • Peptides are short amino acid chains; polypeptides are longer chains that fold into functional proteins, size determines receptor specificity and research use.
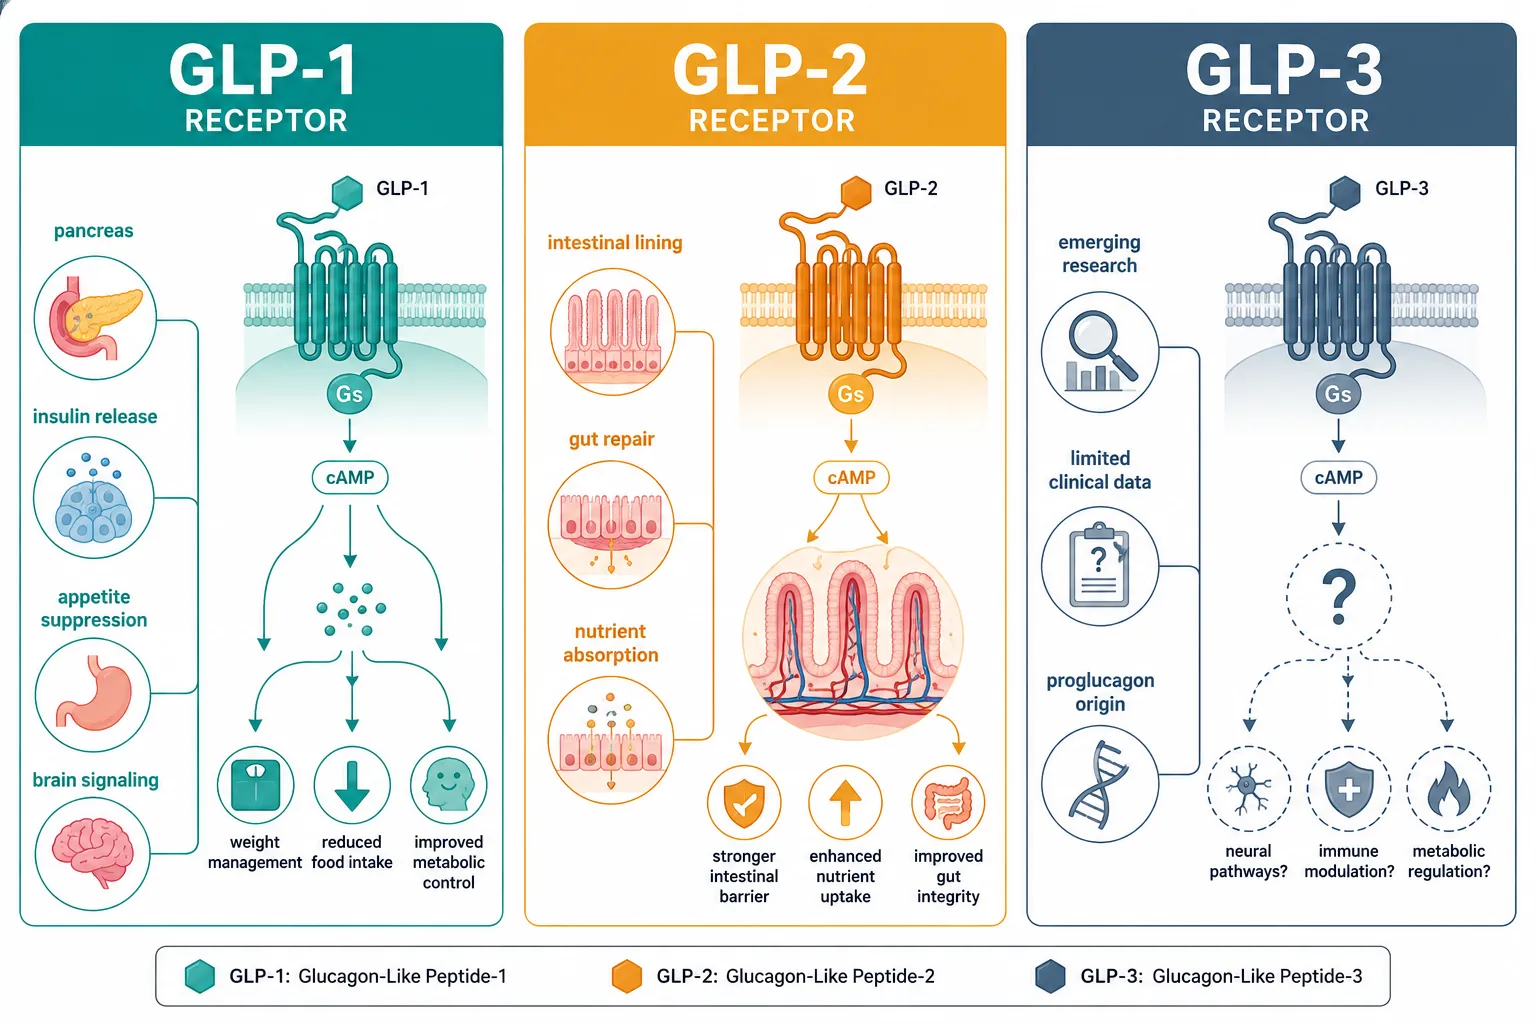
  • GLP-1, GLP-2, and GLP-3 all originate from the same proglucagon gene but act on entirely different receptor systems with distinct biological roles.
  • GLP-1 agonists represent the most clinically active peptide class in 2026, with oral, injectable, and ultra-long-acting formats now available or in late-stage trials.
  • Growth hormone-releasing peptides and analogs operate through the hypothalamic-pituitary axis, making them mechanistically distinct from GLP-class compounds.
  • Purity and structural integrity are non-negotiable in peptide research, third-party testing is the baseline standard.

Understanding Peptide and Polypeptide Structure

Understanding Peptide and Polypeptide Structure

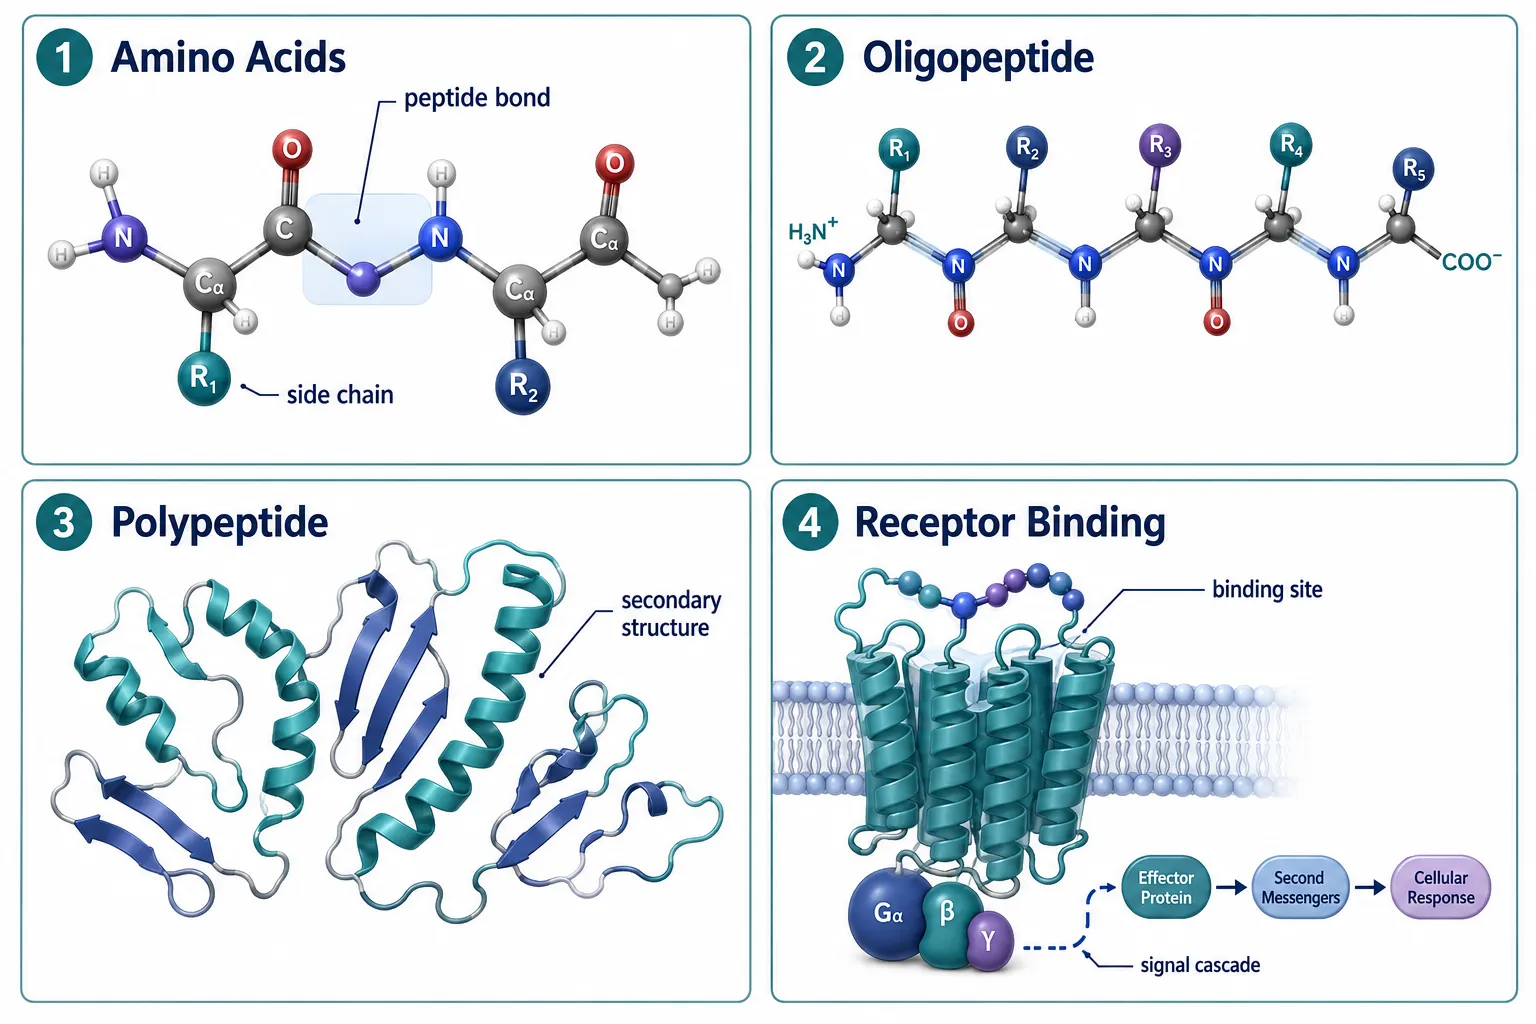
A peptide is any chain of two or more amino acids linked by peptide bonds. The classification system is straightforward:

Term Chain Length Example
Dipeptide 2 amino acids Carnosine
Oligopeptide 3-20 amino acids GLP-1 (30 aa)
Polypeptide 20-50+ amino acids Growth hormone fragments
Protein 50+ amino acids Full-length GH (191 aa)

The distinction matters in research because chain length directly influences receptor selectivity, half-life, and delivery route. Shorter peptides often cross biological barriers more easily but degrade faster. Longer polypeptides may require injectable delivery to preserve their three-dimensional structure.

Receptor binding is the next critical concept. Most research peptides act on G-protein coupled receptors (GPCRs), triggering intracellular signaling cascades rather than directly altering gene expression. This mechanism produces rapid, dose-dependent responses that researchers can measure with precision, a key advantage in preclinical models.

"Peptide size, charge, and secondary structure are not incidental features, they are the mechanism."

For researchers building a broader framework, the top 5 research peptides for metabolic health buyer's guide offers a practical starting point for compound selection within this structural context.

GLP-1, GLP-2, and GLP-3: The Proglucagon Peptide Family

GLP-1, GLP-2, and GLP-3: The Proglucagon Peptide Family

All three glucagon-like peptides derive from a single precursor protein called proglucagon, encoded by the GCG gene. Post-translational processing in different tissues produces distinct peptide fragments with entirely separate biological roles.

GLP-1: The Dominant Research Target

GLP-1 (glucagon-like peptide-1) is a 30-amino-acid incretin hormone secreted by intestinal L-cells. It stimulates insulin secretion, suppresses glucagon, slows gastric emptying, and signals satiety through the central nervous system. These combined actions make it the most studied metabolic peptide in modern pharmacology.

In 2026, the GLP-1 landscape has expanded dramatically:

  • Oral non-peptide GLP-1 agonists such as orforglipron (Foundayo, Eli Lilly) have received approval for chronic weight management, making oral GLP-1 a mainstream modality for the first time.
  • High-dose injectable semaglutide (Wegovy HD, 7.2 mg weekly) extends efficacy for patients requiring greater weight reduction.
  • Ultra-long-acting monthly injectables, including Pfizer's PF-3944/MET-097i, have shown robust Phase 2b results, potentially reducing injection frequency to once per month.
  • Multi-agonist peptides combining GLP-1 with GIP and glucagon receptor activity show the highest weight-loss efficacy seen in late-stage trials to date.

Emerging research also points to non-metabolic applications: addiction neuroscience, mood regulation, and neuroinflammation are active areas of investigation, though these remain speculative outside controlled settings.

Researchers sourcing compounds in this class should review GLP-1 peptide buying: generational research concepts and sourcing notes for structured guidance on acquisition standards. Those evaluating specific product options can also browse GLP-1 peptides available for research.

GLP-2: Intestinal Repair and Nutrient Absorption

GLP-2 is a 33-amino-acid peptide co-secreted with GLP-1 from L-cells. Its receptor is expressed almost exclusively in the gastrointestinal tract. GLP-2 promotes intestinal epithelial growth, reduces gut permeability, and enhances nutrient absorption. Research applications center on short bowel syndrome, inflammatory bowel conditions, and intestinal barrier function.

Researchers working with this compound can find relevant sourcing information under GLP-2 peptide research products.

GLP-3: The Least Characterized Fragment

GLP-3 is a proglucagon-derived fragment whose receptor biology remains incompletely mapped. Public research output on GLP-3 is limited compared to GLP-1 and GLP-2, and no approved therapeutic agents target this peptide as of 2026. It represents an early-stage area where foundational receptor characterization work is still ongoing. Researchers interested in this compound can explore GLP-3 peptide sourcing options as a starting reference.

Growth Hormone Peptides: Axis, Mechanism, and Research Context

Growth Hormone Peptides: Axis, Mechanism, and Research Context

Growth hormone (GH) peptides operate through a fundamentally different axis than GLP-class compounds. The hypothalamic-pituitary-somatotropic axis governs GH release, and research peptides in this category generally work by modulating one or more points along that pathway.

Key categories include:

  • GHRH analogs, mimic growth hormone-releasing hormone to stimulate pulsatile GH secretion from the anterior pituitary. Tesamorelin is the most studied example; researchers can review tesa peptide benefits and research context for a detailed breakdown.
  • GHRPs (growth hormone-releasing peptides), act on ghrelin receptors (GHSR-1a) to amplify GH pulses, often synergistically with GHRH analogs.
  • GH fragments, truncated polypeptide sequences derived from full-length growth hormone, studied for specific downstream effects on fat metabolism and tissue repair.

Downstream from GH release, IGF-1 production in the liver drives many of the tissue-level effects researchers are interested in: protein synthesis, cellular repair, and metabolic substrate utilization. Understanding this cascade is essential for interpreting research data correctly.

Research Standards: Purity, Benchmarking, and Sourcing

The structural complexity of peptides makes quality control non-negotiable. A single incorrect amino acid, oxidized residue, or truncated sequence can produce misleading results or no activity at all.

Minimum standards for research-grade peptides:

  • HPLC purity of 98% or greater
  • Mass spectrometry confirmation of molecular weight
  • Third-party certificate of analysis (CoA) from an independent laboratory
  • Sterility and endotoxin testing for injectable preparations

Reference standards from established manufacturers provide the benchmark against which research samples should be validated. The article on Bachem reference standards and building robust peptide benchmarks outlines how to use certified reference materials effectively.

Researchers should also confirm that suppliers offer lab-tested peptides with verifiable documentation before committing to a source.

Conclusion

The Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides framework presented here gives researchers a reliable map before engaging with any specific compound. The actionable next steps are clear:

  1. Establish structural literacy first, know whether a target peptide is an oligopeptide or polypeptide, and how that affects delivery and receptor interaction.
  2. Match the compound to the correct receptor family, GLP-1, GLP-2, and GLP-3 are not interchangeable despite sharing a common precursor.
  3. Understand the signaling axis, GH peptides require knowledge of the hypothalamic-pituitary cascade to interpret results meaningfully.
  4. Demand verified purity, third-party CoA documentation is the baseline, not a bonus.
  5. Stay current, the GLP-1 field in particular is evolving rapidly, with oral formats, multi-agonists, and monthly injectables reshaping the research landscape throughout 2026 and beyond.

A strong structural foundation makes every downstream research decision more defensible and more productive.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/peptides-and-polypeptides-complete-research-guide-for-glp-1-glp-2-glp-3-and-grow.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-18 13:08:362026-08-18 13:08:36Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides
CJC-1295 With DAC in 2026 Research: Why Long-Acting GHRH Analogs Remain a Core Search Topic

CJC-1295 With DAC in 2026 Research: Why Long-Acting GHRH Analogs Remain a Core Search Topic

August 10, 2026/0 Comments/in Uncategorized/by

Search interest in growth hormone secretagogues has not faded, it has shifted. Researchers and clinicians tracking peptide science in 2026 consistently return to one compound that stands apart from shorter-acting analogs: CJC-1295 with DAC. The persistence of this compound as a core search topic reflects a straightforward pharmacological advantage that newer peptides have not yet displaced.

This article examines why CJC-1295 with DAC in 2026 research continues to attract sustained attention, what the Drug Affinity Complex modification actually does, and how the compound fits into the broader landscape of long-acting GHRH analogs.

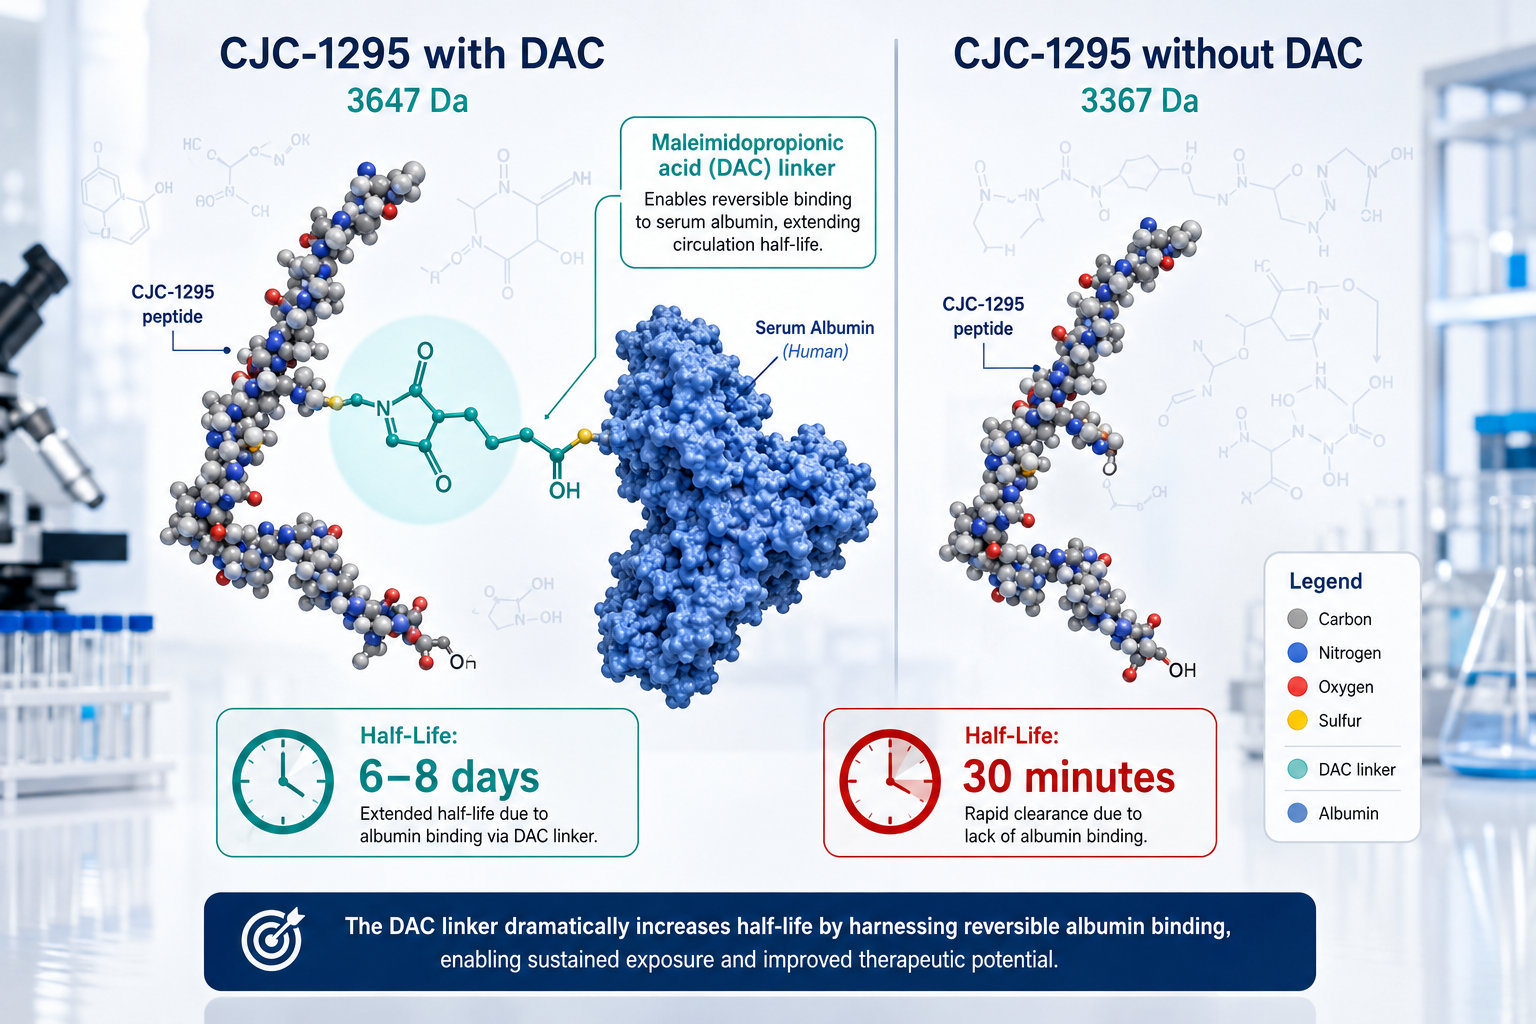
Editorial () infographic-style illustration showing a molecular diagram of the Drug Affinity Complex (DAC) modification

Key Takeaways

  • CJC-1295 with DAC achieves an estimated half-life of 6 to 8 days through albumin binding, making it one of the longest-acting GHRH analogs studied.
  • The Drug Affinity Complex (DAC) modification is the structural feature that separates this compound from standard CJC-1295 without DAC.
  • In 2026, the compound remains unapproved for clinical use in the US and is restricted under compounding regulations, it is strictly a research-use compound.
  • Sustained search volume reflects ongoing interest from researchers studying GH axis modulation, body composition, and metabolic function.
  • Blend formulations combining CJC-1295 with other secretagogues continue to appear in research protocols, expanding the compound's study context.

What the DAC Modification Does, and Why It Matters

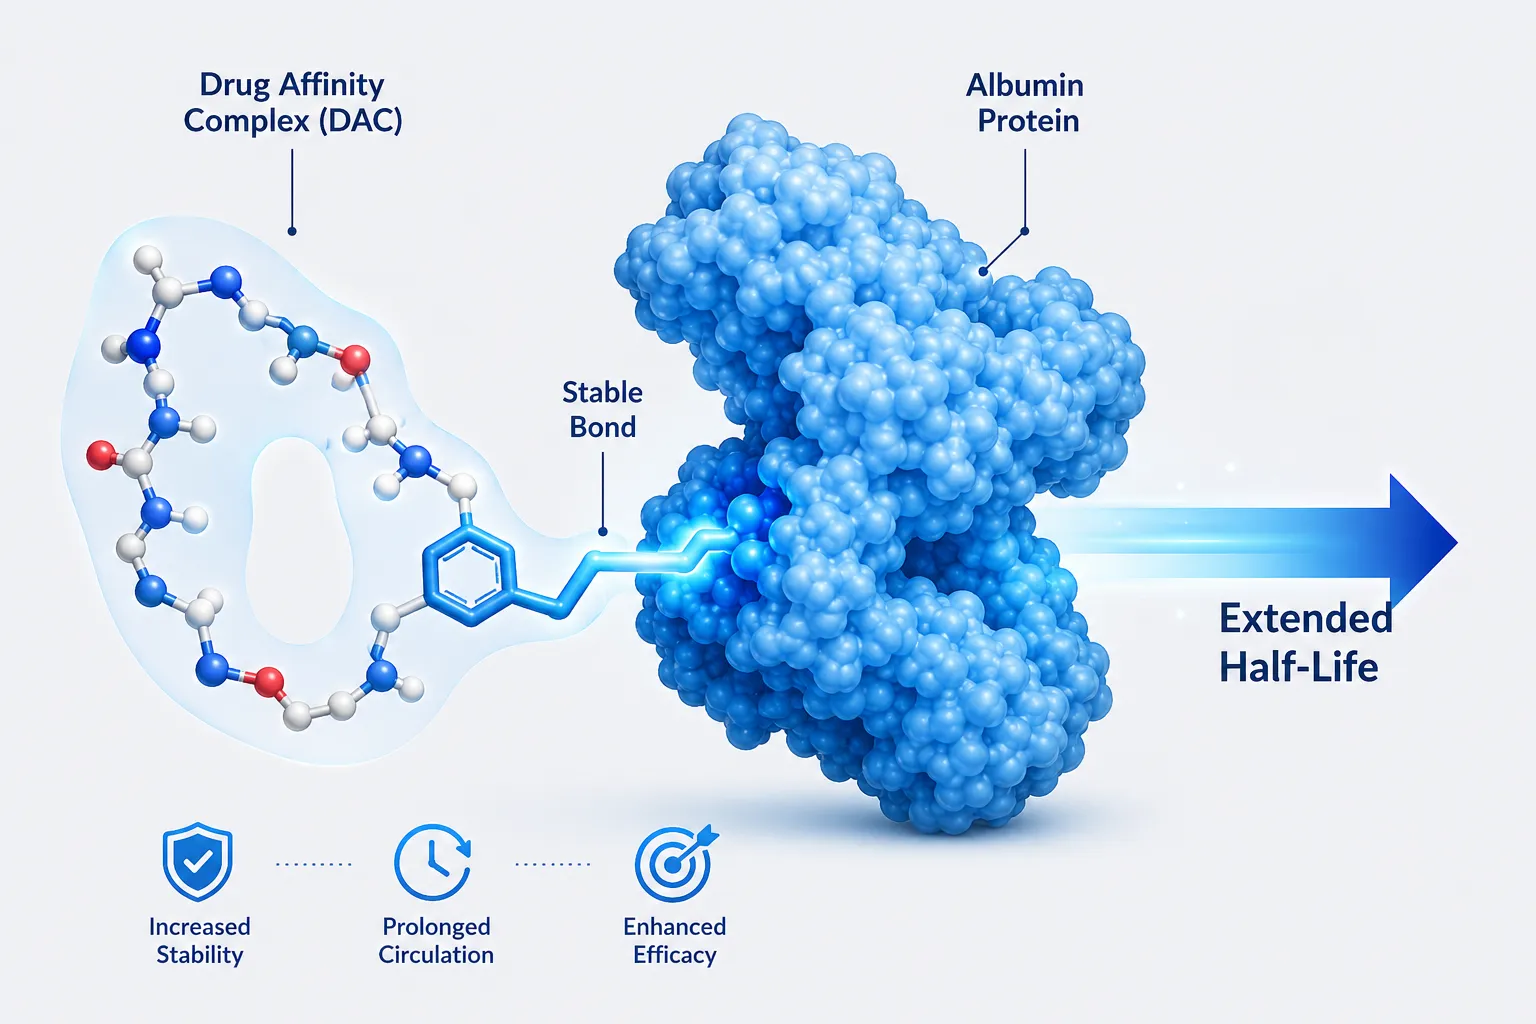
Standard GHRH analogs degrade quickly in circulation. CJC-1295 without DAC, for example, carries a half-life measured in minutes to a few hours. The Drug Affinity Complex modification solves this problem through a reactive maleimide group that forms a covalent bond with circulating serum albumin after injection.

Albumin is the most abundant protein in human plasma. Because the body continuously recycles albumin rather than filtering it rapidly, any peptide bound to albumin inherits a dramatically extended residence time. The result for CJC-1295 with DAC is an estimated half-life of approximately 6 to 8 days, a figure that makes once or twice-weekly dosing theoretically feasible in research protocols rather than daily injections.

This pharmacokinetic profile is the central reason CJC-1295 with DAC in 2026 research remains a reference point. Researchers studying pulsatile versus sustained GH release find the compound useful as a model for long-duration GHRH stimulation. The distinction between pulsatile and continuous GH axis stimulation has meaningful implications for downstream IGF-1 levels, receptor sensitivity, and metabolic outcomes, all active areas of inquiry.

"The albumin-binding strategy used in CJC-1295 with DAC represents one of the cleaner examples of half-life extension through endogenous protein recycling rather than PEGylation or other synthetic approaches."

For researchers exploring adjacent peptide mechanisms, the SS-31 mitochondrial research themes provide a useful contrast: SS-31 operates through entirely different cellular targets, illustrating how varied the peptide research landscape has become.

The 2026 Regulatory Context for Long-Acting GHRH Analogs

Understanding why CJC-1295 with DAC in 2026 research occupies a specific niche requires clarity on its legal status. In the United States, the compound is:

  • Not FDA-approved for any clinical indication
  • Restricted from compounding under current regulatory guidance affecting peptides
  • Available only for legitimate research purposes through licensed research chemical suppliers

This status is not unique to CJC-1295 with DAC. Many peptides that generate significant scientific interest operate in this research-only space. The regulatory environment has, if anything, intensified researcher focus on proper sourcing and documentation.

Researchers working with related secretagogue combinations should review current formulation options such as the Tesamorelin AOD9604 CJC1295 Ipamorelin 12mg blend and the Sermorelin Ipamorelin CJC1295 combination to understand how CJC-1295 is being studied within multi-peptide frameworks.

Why Search Volume for Long-Acting GHRH Analogs Stays High in 2026

Why Search Volume for Long-Acting GHRH Analogs Stays High in 2026

Several converging factors explain why CJC-1295 with DAC in 2026 research continues to generate consistent search traffic rather than fading as older content might suggest.

1. Aging population research interest
Studies on GH axis decline with age remain active. Researchers investigating interventions for age-related changes in lean mass, bone density, and metabolic rate frequently encounter GHRH analogs as a model class.

2. Blend protocol proliferation
CJC-1295 rarely appears in isolation in modern research designs. It is commonly studied alongside Ipamorelin, Tesamorelin, and other secretagogues. The Tesamorelin CJC1295 Ipamorelin 12mg blend and related formulations represent this trend clearly. Each new blend formulation generates fresh search queries tied back to the core compound.

3. Comparative pharmacology interest
Researchers comparing DAC-modified peptides with newer GLP-based compounds, such as those covered in GLP-3 Retatrutide in Phase 3 Trials, often return to CJC-1295 with DAC as a benchmark for sustained receptor stimulation strategies.

4. Half-life as a research design variable
The 6-to-8-day half-life makes CJC-1295 with DAC useful for studies where researchers want stable, prolonged GH axis stimulation without daily intervention. This is a practical research design advantage that shorter-acting compounds cannot replicate.

Feature CJC-1295 Without DAC CJC-1295 With DAC
Half-life ~30 minutes ~6-8 days
Dosing frequency Daily or multiple times daily Once or twice weekly
Albumin binding No Yes (covalent bond)
Research use status (US, 2026) Research only Research only

Researchers sourcing the compound should review the CJC-1295 IPA 10mg product page for current availability and purity documentation standards.

How CJC-1295 With DAC Fits the Broader Peptide Research Landscape

How CJC-1295 With DAC Fits the Broader Peptide Research Landscape

The sustained relevance of CJC-1295 with DAC in 2026 research is not accidental. It reflects a compound that solved a genuine pharmacokinetic problem, short half-life, using an elegant biological mechanism. That solution remains scientifically interesting regardless of how the regulatory environment evolves.

Researchers working across the peptide space will find that the albumin-binding strategy used in DAC modification has influenced thinking in adjacent areas. For context on how peptide-based assay design intersects with modern research frameworks, the overview of carbohydrate antigens and peptide-based assays offers useful background on how peptide structure affects detection and measurement.

The Tesamorelin CJC1295 Ipamorelin 12mg blend reconstitution guide is also a practical resource for researchers handling multi-peptide formulations that include CJC-1295.

Conclusion

CJC-1295 with DAC in 2026 research occupies a durable position in the peptide science conversation for one clear reason: its pharmacokinetic profile is genuinely differentiated. The DAC modification's albumin-binding mechanism extends the compound's half-life to approximately 6 to 8 days, enabling research designs that shorter-acting GHRH analogs cannot support.

Actionable next steps for researchers:

  • Confirm current regulatory status and sourcing requirements before initiating any CJC-1295 with DAC research protocol in 2026.
  • Review blend formulation options to understand how CJC-1295 is being studied in combination with Ipamorelin, Tesamorelin, and other secretagogues.
  • Document purity testing data from suppliers, certificate of analysis standards are a baseline requirement for credible research.
  • Stay current with FDA compounding guidance, as the regulatory landscape for research peptides continues to evolve.

The compound's continued search prominence is earned, not residual. As long as researchers need a model for sustained GHRH stimulation, CJC-1295 with DAC will remain a reference point.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-dac-in-2026-research-why-long-acting-ghrh-analogs-remain-a-core-se.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-10 13:03:552026-08-10 13:03:55CJC-1295 With DAC in 2026 Research: Why Long-Acting GHRH Analogs Remain a Core Search Topic

Tag Archive for: ghrh analogs

CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies

CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies

July 22, 2026/0 Comments/by Pure Tested

Swapping CJC-1295 with DAC for its non-DAC counterpart in a research stack is not a minor formulation tweak, it fundamentally rewrites the pharmacokinetic story. The half-life difference between these two peptides spans roughly five to eight days versus thirty minutes, a gap wide enough to change dosing schedules, alter GH pulsatility, and reshape how researchers design and interpret blend studies. Understanding CJC-1295 with DAC vs. Without DAC: Expanding on Half-Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies is therefore essential before drawing any conclusions from multi-peptide stacks.

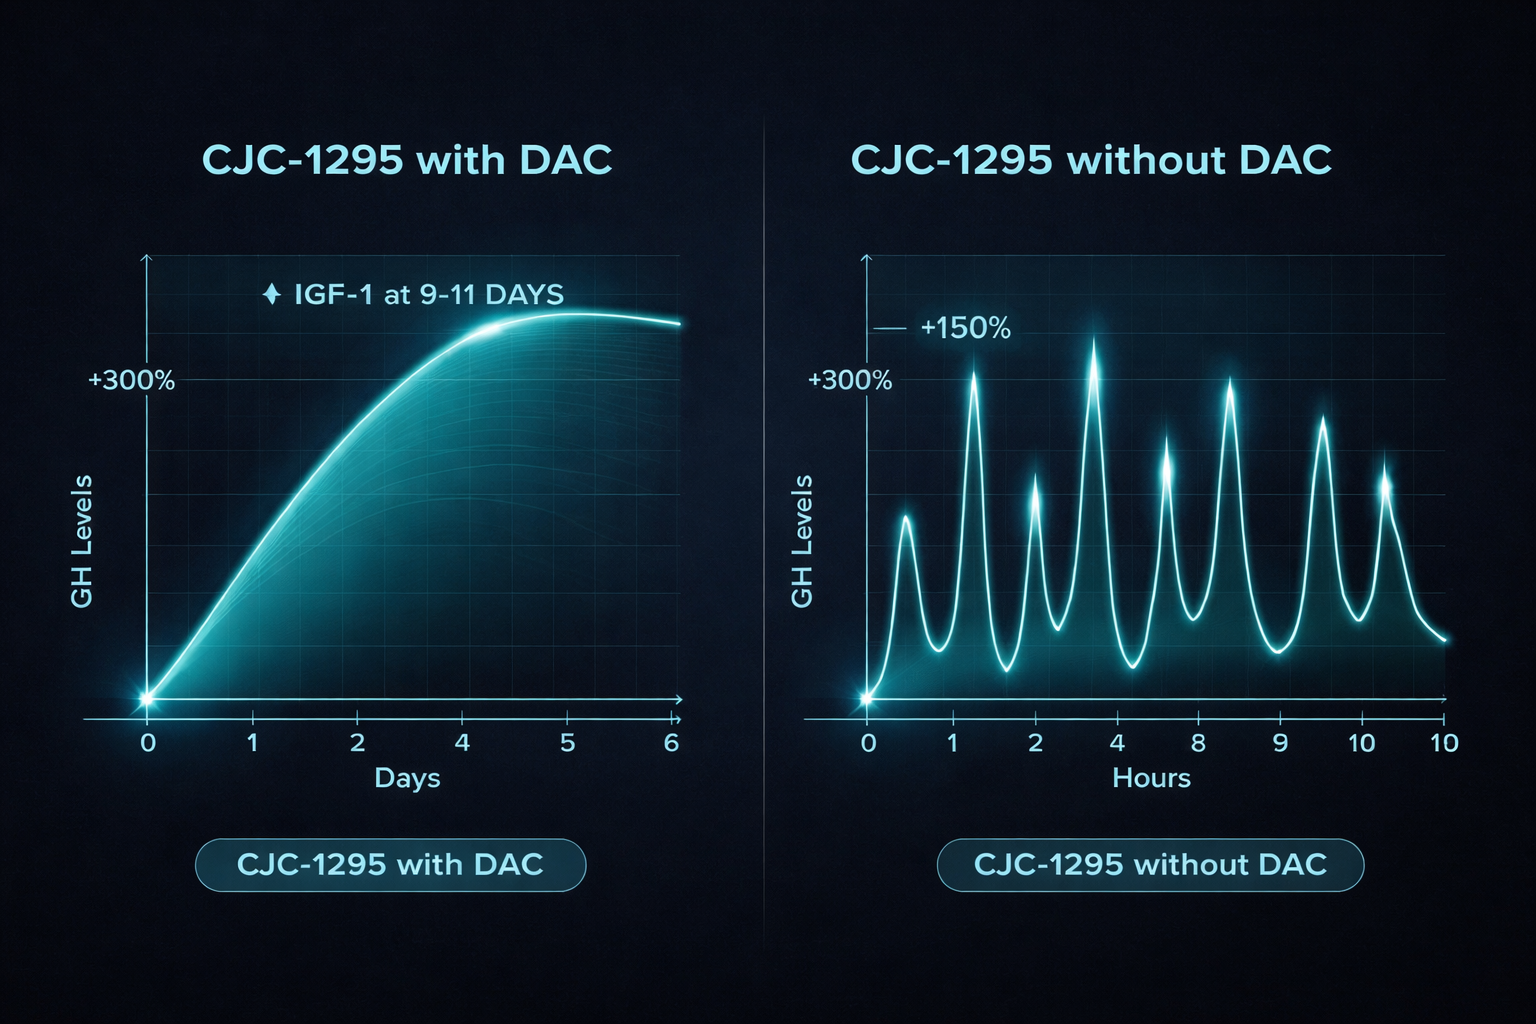
Split-screen infographic illustration () in bright clinical white and cobalt blue: left panel shows a smooth, sustained sine

Key Takeaways

  • CJC-1295 with DAC achieves a half-life of approximately 5.8 to 8.1 days through covalent albumin binding; the non-DAC form lasts roughly 30 minutes in plasma.
  • The DAC moiety uses a maleimidopropionic acid linker to "hitchhike" on serum albumin, which itself persists for 19 to 21 days in humans.
  • No published human pharmacokinetic profile exists for CJC-1295 without DAC; its half-life is inferred rather than directly measured.
  • In tesa-CJC-1295-ipamorelin blend research, the choice of DAC or non-DAC form determines whether GH output is a sustained basal elevation or a series of short pulses.
  • Dosing frequency, study design, and safety monitoring must be adapted separately for each form, data from DAC trials cannot be applied to non-DAC protocols.

The Mechanism Behind the Half-Life Gap

The entire pharmacokinetic difference between the two forms traces back to a single chemical addition: the Drug Affinity Complex (DAC) moiety. This maleimidopropionic acid linker covalently binds to serum albumin after injection. Because albumin circulates in the bloodstream for 19 to 21 days, any peptide attached to it inherits a dramatically extended lifespan. The result is a half-life of 5.8 to 8.1 days for CJC-1295 with DAC in healthy adults, compared with roughly 30 minutes for the non-DAC peptide.

The non-DAC form, structurally similar to tetrasubstituted modified GRF 1-29, does carry amino acid substitutions that resist dipeptidyl peptidase-4 (DPP-4) cleavage. This resistance extends its survival beyond native GHRH's two-minute plasma half-life, but without albumin binding, clearance still occurs within half an hour. Critically, no direct human pharmacokinetic measurement for CJC-1295 without DAC has been published as of mid-2026. The 30-minute estimate is inferred from DPP-4 resistance data and the known absence of albumin binding, not from a controlled PK trial.

For a detailed breakdown of the albumin-binding mechanism and its downstream effects on IGF-1, see this deeper dive into CJC-1295 with DAC research findings.

"Extrapolating DAC-trial data to the non-DAC peptide is pharmacokinetically invalid, the multi-day duration is unique to the DAC modification."

Modeling Pharmacokinetics in Common Research Stacks

CJC-1295 with DAC vs. Without DAC: How the Tesamorelin and Ipamorelin Blend Changes the Picture

CJC-1295 with DAC vs. Without DAC: How the Tesamorelin and Ipamorelin Blend Changes the Picture

Tesamorelin is an FDA-approved GHRH analog with a relatively short plasma half-life, making it a useful pharmacokinetic comparator when modeling blend behavior. In a tesa-CJC-1295-ipamorelin stack, the choice of DAC or non-DAC CJC-1295 produces two very different GH output profiles.

With DAC in the blend:

  • CJC-1295 with DAC provides a continuous, low-level GHRH signal lasting several days per injection.
  • Ipamorelin, a selective GHRP with a half-life of roughly two hours, adds superimposed short pulses on top of this basal elevation.
  • The combined effect is a sustained GH baseline with intermittent amplified peaks.
  • IGF-1 can remain above baseline for up to 28 days after multiple doses, which has significant implications for study endpoints and washout periods.

Without DAC in the blend:

  • Non-DAC CJC-1295 acts as a brief GHRH burst, peaking and clearing within 30 minutes.
  • Ipamorelin's pulses align temporally with these short GHRH windows, creating a synchronized but transient GH spike.
  • The overall GH profile more closely resembles physiologic pulsatility.
  • Researchers studying tesa alongside this form are effectively comparing two short-acting GHRH analogs rather than a long-acting versus short-acting pair.

For researchers exploring blend formulations, the tesa-CJC-1295-ipamorelin 12mg blend and the tesa-AOD9604-CJC-1295-ipamorelin blend illustrate how component selection shapes the overall protocol design.

A comparison of tesa's standalone pharmacokinetics versus ipamorelin's is also covered in this ipamorelin vs. tesa overview, which helps contextualize blend behavior further.

Dosing Schedules, GH Pulsatility, and Study Design Implications

Applying CJC-1295 with DAC vs. Without DAC Half-Life Differences to Protocol Planning

Applying CJC-1295 with DAC vs. Without DAC Half-Life Differences to Protocol Planning

The half-life gap directly dictates dosing frequency. CJC-1295 with DAC supports once- or twice-weekly injection schedules while maintaining sustained GH and IGF-1 elevation between doses. Non-DAC CJC-1295, by contrast, requires daily or multiple-daily dosing to maintain any meaningful GHRH presence.

Feature CJC-1295 with DAC CJC-1295 without DAC
Plasma half-life 5.8 to 8.1 days Approx. 30 minutes (inferred)
Albumin binding Yes (covalent) No
GH output pattern Sustained basal elevation Short pulsatile burst
Recommended dosing frequency Once or twice weekly Daily or multiple times daily
Human PK data available Yes (Phase 1 trial data) No direct measurement

Key study design considerations include:

  • Washout periods: The DAC form requires washout periods of several weeks due to prolonged IGF-1 elevation; non-DAC washout is far shorter.
  • Pulsatility preservation: Researchers prioritizing physiologic GH pulse patterns should favor non-DAC CJC-1295 or tesa as the GHRH component.
  • Blunted pulsatility risk: The sustained flat GH signal from CJC-1295 with DAC may suppress normal GH pulsatility, an endocrinological consideration absent from short-acting protocols.
  • Endpoint timing: IGF-1 measurements taken at 24 hours post-dose will reflect very different biological states depending on which form is used.

For researchers examining the CJC-1295 with DAC profile in greater depth, this CJC-1295 with DAC deeper dive and the sermorelin-ipamorelin-CJC-1295 combination overview provide additional context on how half-life interacts with GHRP co-administration.

Conclusion

The core lesson from examining CJC-1295 with DAC vs. Without DAC: Expanding on Half-Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies is straightforward: these are not interchangeable peptides with minor formulation differences. The DAC moiety transforms a 30-minute compound into a multi-day one, and that transformation cascades into every aspect of blend design, from dosing frequency and GH pulsatility to washout periods and safety monitoring.

Actionable next steps for researchers:

  1. Define the desired GH output pattern first, sustained basal elevation or pulsatile bursts, before selecting the CJC-1295 form.
  2. Never apply DAC-derived pharmacokinetic data to non-DAC protocols; treat them as separate compounds.
  3. When designing tesa-CJC-1295-ipamorelin blend studies, account for the dramatically different washout requirements between DAC and non-DAC variants.
  4. Consult current tesa dosing and pharmacokinetic guidance to calibrate expectations when tesa serves as the GHRH comparator.
  5. Review the GH axis product line overview for a broader perspective on how each component fits within a well-structured research protocol.

Rigorous protocol design begins with understanding the pharmacokinetics of each component individually, only then can blend behavior be accurately modeled and interpreted.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/cjc-1295-with-dac-vs-without-dac-expanding-on-half-life-differences-using-tesamo.webp 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-22 13:05:412026-07-27 13:32:21CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design

CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design

June 21, 2026/0 Comments/by Pure Tested

A single structural modification — the addition of a Drug Affinity Complex linker — transforms a short-acting peptide into one with a half-life measured in days rather than minutes. That pharmacokinetic gap sits at the heart of the debate around CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design, and it shapes every variable a researcher must account for when designing a growth hormone (GH) study.

Key Takeaways

  • CJC-1295 with DAC binds covalently to serum albumin, extending its half-life to approximately 6-8 days.
  • CJC-1295 without DAC (Mod GRF 1-29) has a half-life of roughly 30 minutes and produces pulsatile GH release.
  • The DAC variant sustains GH elevation but may disrupt natural pulsatile secretion and risk receptor desensitization.
  • Experimental design choices — dosing frequency, combination partners, and outcome measures — differ significantly between the two forms.
  • Researchers often pair CJC-1295 without DAC with GHRPs like Ipamorelin to closely mimic physiological GH rhythms.

Key Takeaways

The Molecular Difference: What DAC Actually Does

The Drug Affinity Complex (DAC) is a maleimidopropionic acid linker attached to the C-terminus of CJC-1295. This addition allows the peptide to form a covalent bond with the Cys34 residue of serum albumin, effectively anchoring it to a long-lived carrier protein circulating in the bloodstream.

The result is a meaningful increase in molecular weight — from approximately 3,367 Da (without DAC) to roughly 3,647 Da (with DAC) — and a dramatic extension of circulating half-life.

Feature CJC-1295 with DAC CJC-1295 without DAC
Half-life ~6-8 days ~30 minutes
Molecular weight ~3,647 Da ~3,367 Da
Albumin binding Covalent (Cys34) None
GH release pattern Sustained, continuous Pulsatile, transient
Dosing frequency Once or twice weekly Multiple times daily

For researchers exploring CJC-1295 research findings, understanding this structural distinction is the essential first step before any protocol is designed.


GH Secretion Patterns: Sustained Elevation vs. Physiological Pulses

GH Secretion Patterns: Sustained Elevation vs. Physiological Pulses

The pharmacokinetic difference between the two variants produces fundamentally different growth hormone secretion profiles, each with distinct research implications.

CJC-1295 with DAC: Continuous Stimulation

Clinical data from Phase I and II trials conducted in the mid-2000s showed that a single dose of CJC-1295 with DAC produced a 2-10 fold increase in GH levels lasting up to six days. IGF-1 levels remained elevated for 9-11 days following that single administration. This sustained profile makes the DAC variant well-suited for studies requiring prolonged GH elevation without frequent dosing.

However, continuous GH stimulation carries a notable concern: receptor desensitization. Prolonged activation of GHRH receptors may reduce their sensitivity over time, potentially blunting the GH response in longer-term protocols.

CJC-1295 without DAC: Mimicking Natural Rhythms

CJC-1295 without DAC — also called Mod GRF 1-29 — produces short, sharp GH pulses that closely mirror the body's natural pulsatile secretion pattern. This pulsatility is considered important for maintaining insulin sensitivity and preserving receptor responsiveness.

"Pulsatile GH release is not merely a physiological quirk — it is a functional requirement for downstream signaling fidelity."

Researchers focused on physiological accuracy tend to favor the non-DAC variant. It is frequently combined with growth hormone-releasing peptides (GHRPs) such as Ipamorelin to amplify pulsatile release. The Sermorelin, Ipamorelin, and CJC-1295 combination represents a common multi-peptide research approach built on this principle. Similarly, Ipamorelin and Sermorelin stack research provides additional context for synergistic GHRH-GHRP protocols.


Experimental Design Considerations for Each Variant

Experimental Design Considerations for Each Variant

Choosing between these two forms in a research context is not simply a matter of convenience — it determines the biological question the experiment can validly answer.

When to Use the DAC Variant

  • Studies examining sustained GH elevation and downstream IGF-1 responses
  • Protocols where infrequent dosing (once or twice weekly) is operationally necessary
  • Research into conditions historically linked to GH deficiency, reflecting the peptide's Phase II trial history

When to Use the Non-DAC Variant

  • Protocols designed to replicate natural pulsatile GH secretion
  • Studies assessing receptor sensitivity over time
  • Combination research with GHRPs, where timing and pulse synchronization matter

For researchers also exploring related GHRH analogs, comparing Tesamorelin vs. Sermorelin offers useful pharmacokinetic context. The Tesamorelin and CJC-1295 blend research further illustrates how multi-peptide designs can address complex GH axis questions. Researchers interested in body composition outcomes may also find the Tesamorelin body composition research themes page a valuable reference point.

Dosing frequency is perhaps the most practical design variable. The DAC variant's weekly schedule reduces protocol complexity, while the non-DAC variant's multiple-daily-injection requirement demands tighter experimental control but yields data more reflective of physiological GH dynamics.


Conclusion

The comparison of CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design ultimately comes down to one core question: does the research require sustained GH elevation or physiological pulsatility?

The DAC variant offers convenience and prolonged action through albumin binding, making it appropriate for sustained-elevation protocols. The non-DAC variant preserves natural GH rhythm, reduces receptor desensitization risk, and pairs effectively with GHRPs for synergistic research designs.

Actionable next steps for researchers in 2026:

  1. Define the GH secretion profile your study requires before selecting a variant.
  2. Account for dosing frequency in your experimental timeline and resource planning.
  3. Consider combination protocols with verified GHRPs when pulsatile secretion fidelity is the priority.
  4. Review available CJC-1295 research findings and related blend data to inform protocol selection.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/CJC-1295-with-DAC-vs.-Without-DAC-Impact-on-Growth-Hormone-Secretion-and-Experimental-Design.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-21 13:07:122026-07-20 15:02:36CJC-1295 with DAC vs. Without DAC: Impact on Growth Hormone Secretion and Experimental Design
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top