Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: glp-class peptides

Prednisone and Peptide Immunomodulation: How Classic Steroids Compare With BPC-157, GHK-Cu, and GLP-Class Peptides in Inflammatory Research

Prednisone and Peptide Immunomodulation: How Classic Steroids Compare With BPC-157, GHK-Cu, and GLP-Class Peptides in Inflammatory Research

September 20, 2026/0 Comments/in Uncategorized/by

More than 30 million prescriptions for oral corticosteroids are written annually in the United States alone, yet a growing body of bench research is asking whether peptide-based compounds might one day complement or refine how science approaches inflammatory signaling. The field of prednisone and peptide immunomodulation: how classic steroids compare with BPC-157, GHK-Cu, and GLP-class peptides in inflammatory research sits at an important crossroads between established pharmacology and early-stage discovery science.

This article examines the mechanistic differences between glucocorticoid immunosuppression and peptide-mediated tissue modulation, strictly within the context of preclinical and translational research models.

Key Takeaways

  • Prednisone is a well-characterized glucocorticoid with a defined mechanism, extensive clinical data, and regulatory approval for dozens of inflammatory conditions.
  • BPC-157 shows consistent anti-inflammatory signals in animal models but has zero completed, peer-reviewed human efficacy trials as of 2026.
  • GHK-Cu demonstrates immunomodulatory activity in zebrafish and mouse models, with no human randomized trial data for inflammatory indications.
  • GLP-class peptides intersect metabolic and inflammatory pathways in emerging research, representing a distinct mechanistic category from classical steroids.
  • Evidence gaps between preclinical promise and clinical validation remain the defining challenge across all peptide candidates reviewed here.

How Prednisone Suppresses Inflammation: The Glucocorticoid Benchmark
How Prednisone Suppresses Inflammation: The Glucocorticoid Benchmark

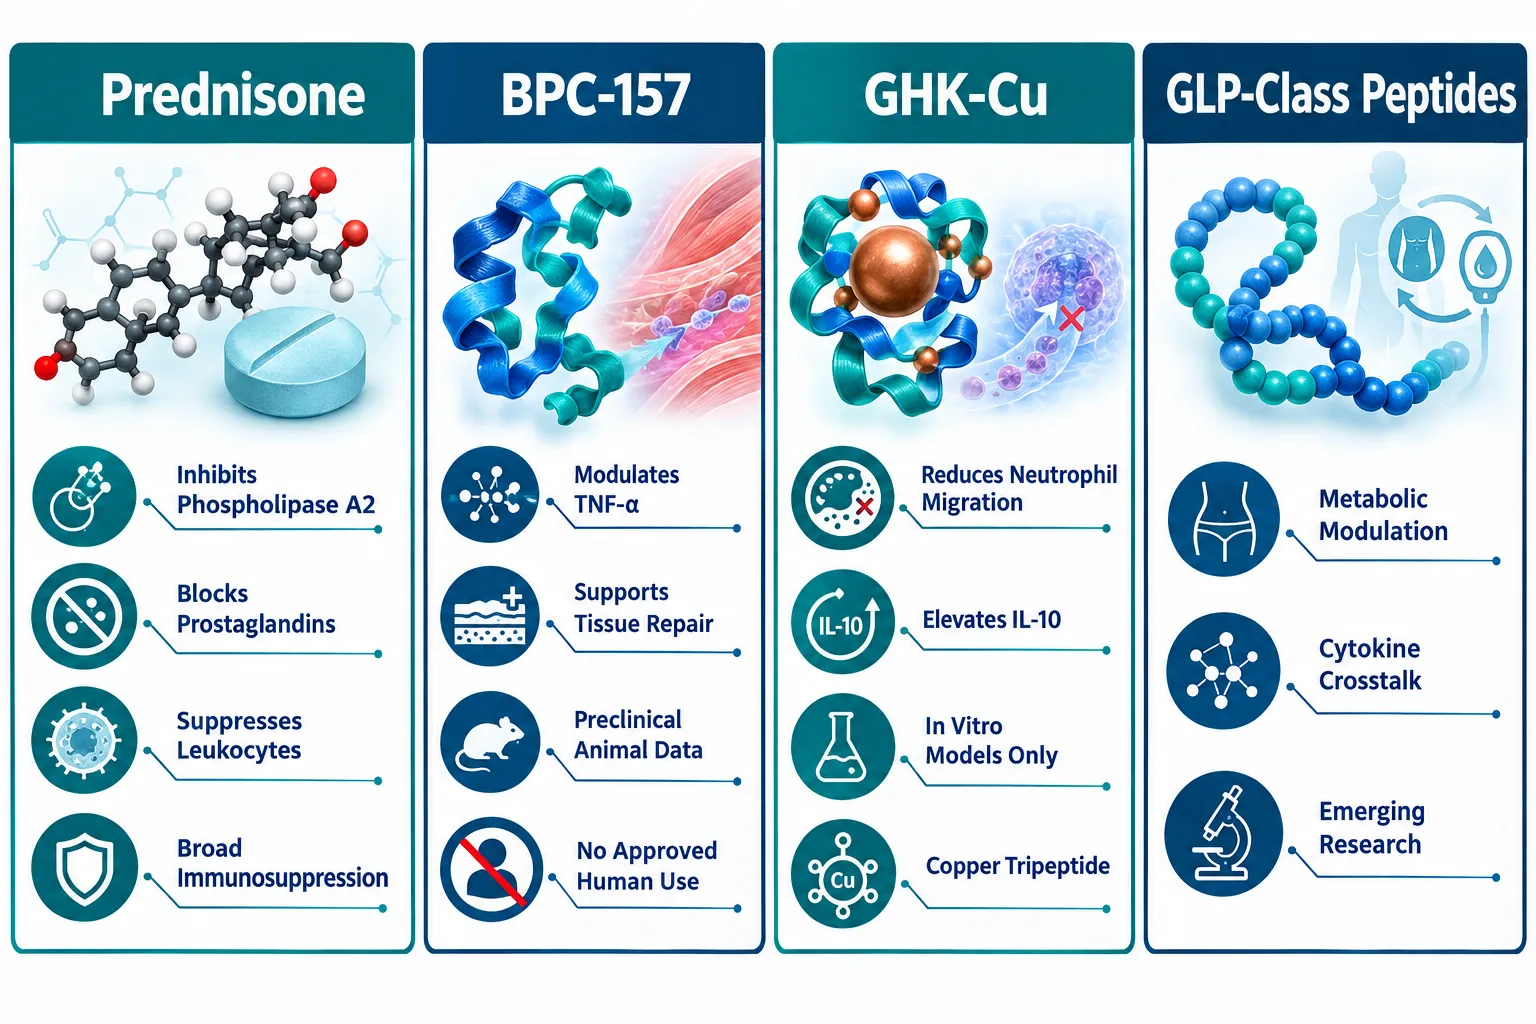
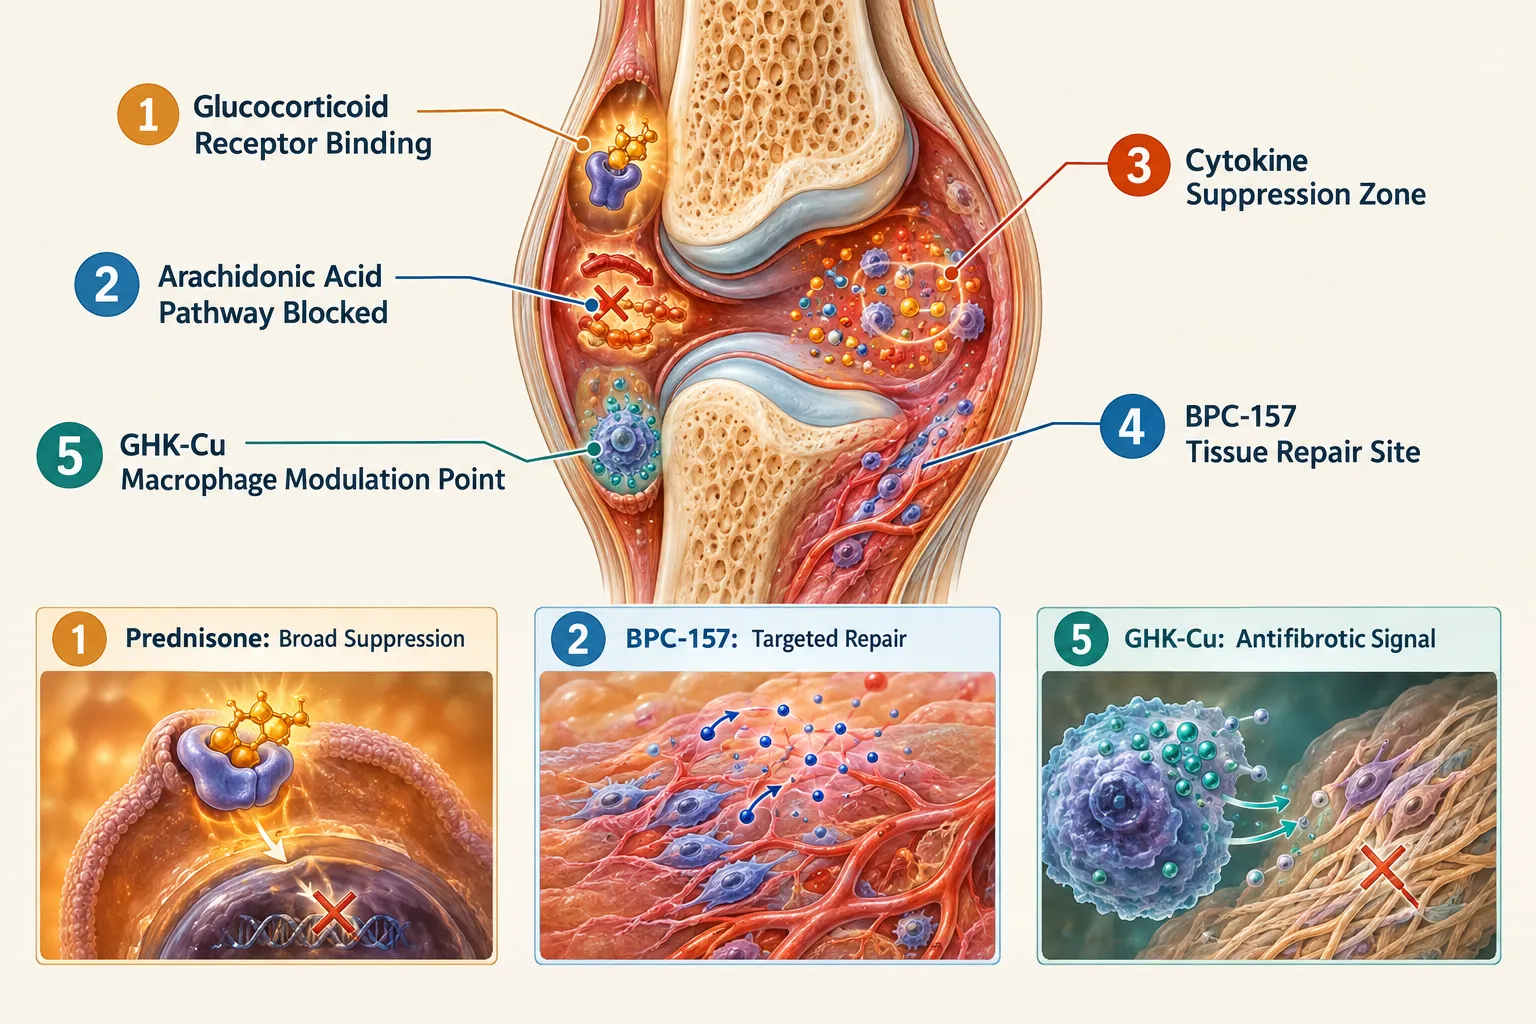
Prednisone functions as a prodrug, converting to prednisolone in the liver before exerting its effects. As a prototypical glucocorticoid, it suppresses inflammation through several well-documented pathways. It inhibits phospholipase A2, blocking the release of arachidonic acid and thereby reducing downstream production of both prostaglandins and leukotrienes. It also suppresses polymorphonuclear leukocyte migration and reverses increased capillary permeability, two hallmarks of acute tissue inflammation.

These mechanisms are broad by design. Prednisone does not selectively target one cytokine or one tissue type; it modulates the inflammatory response systemically. A 2025 translational analysis published in Theranostics added important nuance: RNA-sequencing data showed that prednisolone was most effective at reducing brain inflammatory signaling pathways in a CNS inflammation model, while prednisone itself had no significant effect on inflammation-related signaling in that specific tissue context. This finding underscores that even within the glucocorticoid class, tissue-specific immunomodulation varies considerably.

What makes prednisone the benchmark for comparison?

  • Decades of pharmacokinetic and pharmacodynamic data
  • Defined dose-response relationships across multiple inflammatory conditions
  • Established risk-benefit frameworks including adrenal suppression, bone density effects, and metabolic consequences
  • Regulatory approval and clinical guideline integration worldwide

This depth of evidence is precisely what makes it a useful comparator when evaluating emerging peptide candidates.

BPC-157 and GHK-Cu: Preclinical Signals and Evidence Gaps
BPC-157 and GHK-Cu: Preclinical Signals and Evidence Gaps

BPC-157: Tissue Repair Peptide With a Thin Human Evidence Base

BPC-157 is a synthetic 15-amino-acid peptide derived from a protein found in gastric juice. In preclinical models, it has demonstrated the ability to significantly decrease pro-inflammatory cytokines including TNF-α, IL-6, and IFN-γ, while also supporting tissue repair across musculoskeletal, gastrointestinal, and neurological animal models. More than 100 animal studies have explored its properties.

However, the human evidence picture is starkly different. A 2025 systematic review synthesized 36 studies, 35 of which were animal studies and one was an uncontrolled human chart review, and found zero completed controlled human efficacy trials. Available human data consist of three small pilot studies covering intra-articular knee pain, interstitial cystitis, and an intravenous safety and pharmacokinetics study in two healthy adults at doses up to 20 mg. These studies primarily demonstrate short-term tolerability rather than proven efficacy.

The most notable human signal comes from an unpublished Croatian Phase II study in 53 adults with mild-to-moderate ulcerative colitis. A 40 mL enema containing 80 mg BPC-157 once daily for 14 days reportedly yielded 38% clinical remission at week 4 versus 13% with placebo. Because the full study report, statistical analysis plan, and longer-term follow-up data were never published, regulators classify this evidence as "very low certainty." BPC-157 currently holds no FDA approval for any indication and no publicly listed IND authorization for inflammation. Researchers interested in peptide dosing protocols should note that optimal dosing, systemic adverse effects, and comparative effectiveness versus glucocorticoids remain undefined in humans.

One active development is a 120-patient Phase 2 double-blind, placebo-controlled study of injectable BPC-157 for grade II hamstring strain, but no efficacy outcomes have been reported publicly as of mid-2026.

GHK-Cu: Copper Tripeptide With Antifibrotic and Anti-Inflammatory Signals

GHK-Cu (glycine-histidine-lysine copper) offers a mechanistically distinct profile. A 2026 zebrafish larvae model of chemically induced inflammation showed that GHK-Cu reduced both neutrophil and macrophage migration, lowered pro-inflammatory cytokines, and increased the anti-inflammatory cytokine IL-10. A 2024 mouse model of silicosis found that GHK-Cu attenuated lung inflammation and fibrosis, identifying peroxiredoxin-6 (PRDX6) as a molecular binding target, with no significant systemic toxicity at tested doses.

Researchers exploring GHK-Cu peptides for sale for laboratory use should understand that current evidence remains restricted to animal and in vitro models. No human randomized trials or dose-finding studies exist for inflammatory indications.

GLP-Class Peptides and the Broader Landscape of Peptide Immunomodulation

GLP-Class Peptides and the Broader Landscape of Peptide Immunomodulation

GLP-class peptides represent a distinct mechanistic category within the broader field of prednisone and peptide immunomodulation: how classic steroids compare with BPC-157, GHK-Cu, and GLP-class peptides in inflammatory research. Originally characterized for their metabolic roles in glucose homeostasis and satiety signaling, GLP-class compounds are now being studied for their intersection with inflammatory cytokine networks. Research models suggest that GLP receptor activation can modulate macrophage polarization and reduce systemic inflammatory markers, creating a potential bridge between metabolic and immune regulation.

Those following developments in this space can explore research-grade options such as GLP-3 peptide for sale or the GLP-3R 10mg peptide GA10 for laboratory investigation. Additional GLP-class compounds are catalogued under GLP-3 peptides for sale for researchers tracking this category.

Research Perspective: The mechanistic gap between glucocorticoid broad-spectrum immunosuppression and peptide-targeted tissue modulation is not simply a matter of potency, it reflects fundamentally different biological strategies. Steroids suppress; some peptides appear to redirect or repair.

Comparing the Evidence Tiers

Compound Primary Mechanism Human Trial Data Regulatory Status
Prednisone Phospholipase A2 inhibition, broad immunosuppression Extensive RCT database FDA-approved, multiple indications
BPC-157 Cytokine modulation, tissue repair 3 pilot studies, no efficacy RCTs No approval, experimental
GHK-Cu Neutrophil/macrophage modulation, antifibrotic None (animal/in vitro only) No approval, research stage
GLP-class Metabolic-immune crosstalk Metabolic indications only Approved for metabolic use; inflammatory use experimental

For researchers sourcing compounds across multiple peptide categories, working with a best peptide supplier that provides verified purity documentation is essential for maintaining experimental integrity.

Conclusion

The comparison at the heart of prednisone and peptide immunomodulation: how classic steroids compare with BPC-157, GHK-Cu, and GLP-class peptides in inflammatory research reveals a fundamental asymmetry in the evidence base. Prednisone operates within a thoroughly characterized pharmacological framework built over decades of clinical research. BPC-157 and GHK-Cu show genuine mechanistic interest in preclinical models, but neither has cleared the threshold of controlled human efficacy data. GLP-class peptides occupy a third lane, metabolically validated but with inflammatory applications still in early research phases.

Actionable next steps for researchers and science communicators:

  • Treat BPC-157 and GHK-Cu findings as hypothesis-generating, not practice-defining, until controlled human trials are completed and published.
  • Monitor the ClinicalTrials.gov registry for emerging Phase 2 and Phase 3 peptide trials that may shift the evidence landscape in the next three to five years.
  • When sourcing research-grade peptides, prioritize suppliers with third-party purity verification and transparent certificates of analysis.
  • Recognize that mechanistic novelty in animal models does not translate automatically to clinical equivalence with established agents like prednisone.

The science is moving, but the evidence must lead.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prednisone-and-peptide-immunomodulation-how-classic-steroids-compare-with-bpc-15.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-20 13:06:152026-09-20 13:06:15Prednisone and Peptide Immunomodulation: How Classic Steroids Compare With BPC-157, GHK-Cu, and GLP-Class Peptides in Inflammatory Research
Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research

Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research

September 12, 2026/0 Comments/in Uncategorized/by

Nearly one in eight men will receive a prostate cancer diagnosis during their lifetime, making prostate-specific antigen one of the most scrutinized biomarkers in all of medicine. As research into hormone-modulating compounds accelerates, particularly selective estrogen receptor modulators like enclomiphene and polypeptide agents such as GLP-1 and GLP-3 analogs, laboratories and clinicians face a practical question: how does PSA monitoring integrate with these newer interventions? Understanding Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research is no longer a niche concern; it sits at the intersection of endocrinology, oncology safety, and advanced peptide science.

Key Takeaways

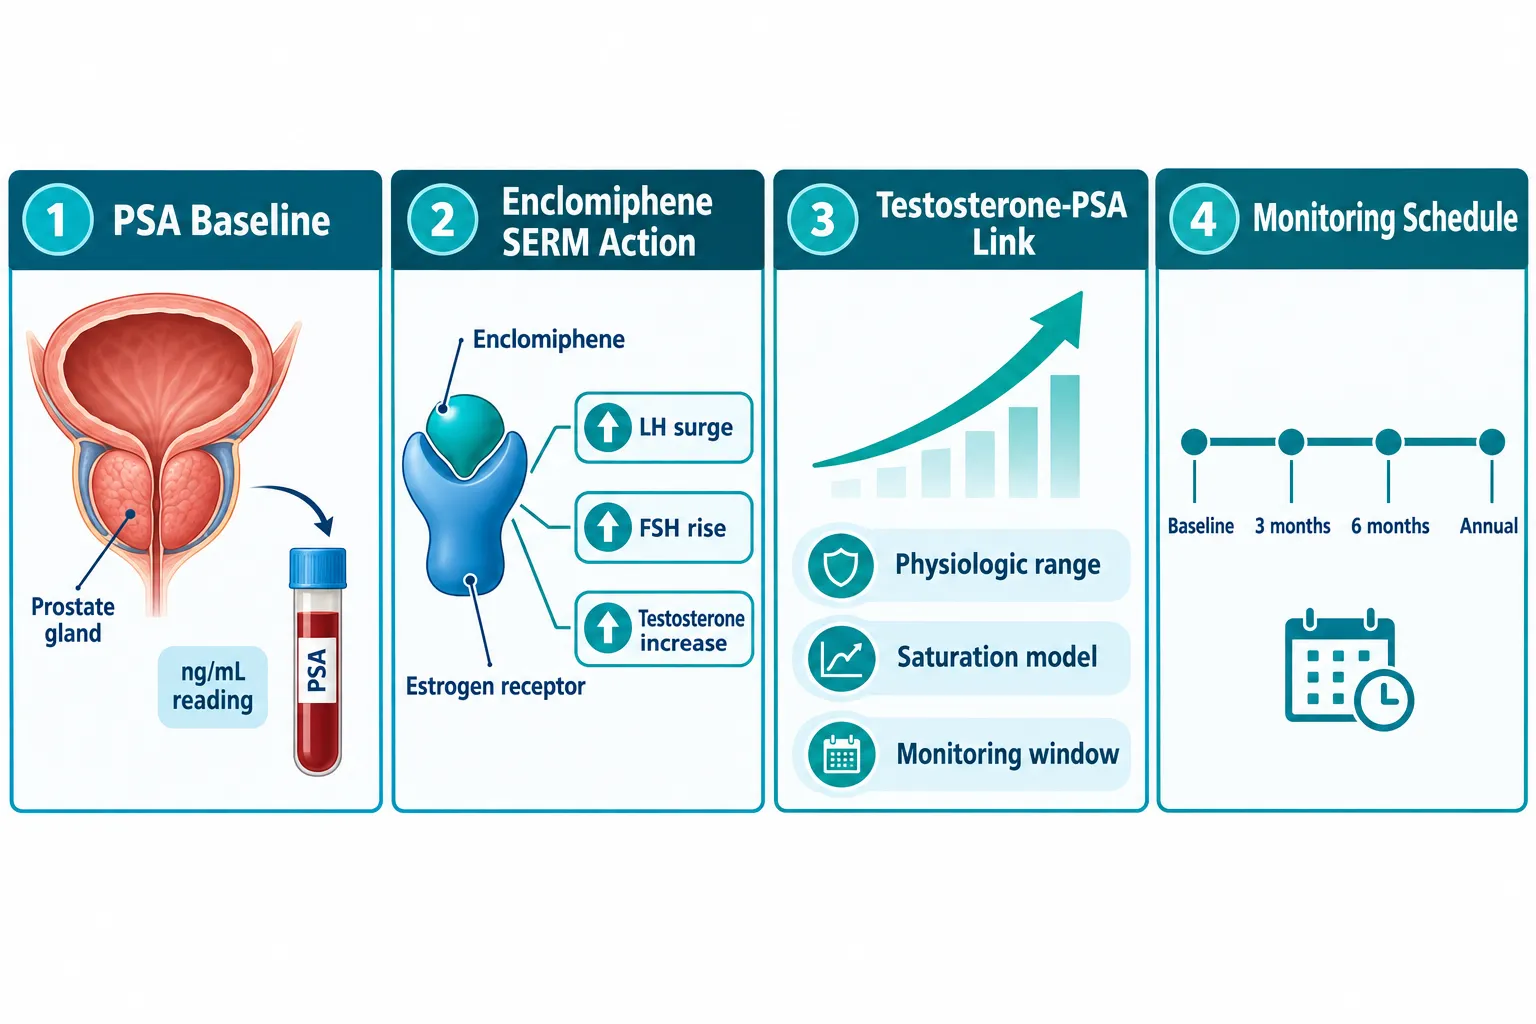
  • PSA is a serine protease produced by prostate epithelium; any intervention that raises testosterone, including enclomiphene, can modestly influence PSA values.
  • Phase III enclomiphene trials have not demonstrated a statistically significant increase in PSA or a clear prostate cancer signal compared with placebo.
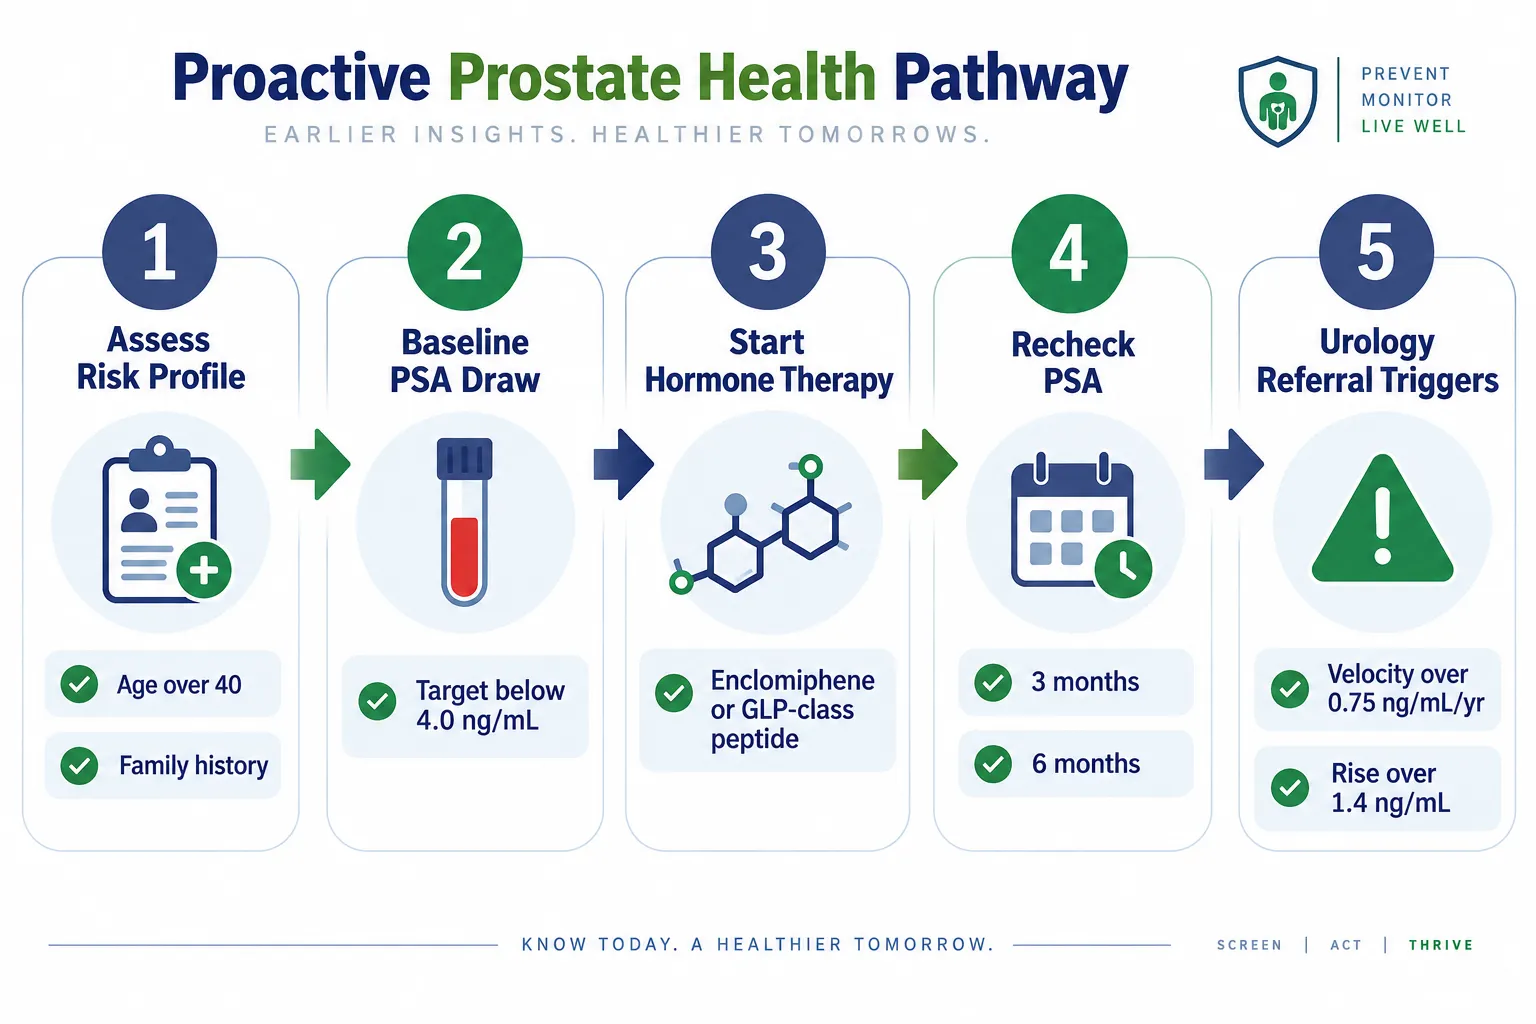
  • Standard monitoring practice mirrors testosterone-replacement protocols: baseline PSA, repeat at 3 and 6 months, then periodic review.
  • GLP-class peptides (GLP-1, GLP-3 analogs such as retatrutide) are not currently integrated into PSA-specific monitoring frameworks; their research focus remains metabolic and cardiovascular.
  • PSA monitoring functions as a safety net, not as evidence that hormone-modulating therapy causes prostate cancer.

What Is PSA and Why Does Hormone Status Matter

What Is PSA and Why Does Hormone Status Matter

Prostate-specific antigen is a serine protease encoded by the KLK3 gene and secreted almost exclusively by prostate epithelial cells. Its primary physiologic role is liquefying seminal fluid, but because it leaks into circulation in proportion to prostate tissue volume and disruption, serum PSA has become the standard screening tool for prostate pathology.

Why does testosterone matter to PSA? Androgen receptors in prostate tissue directly regulate KLK3 transcription. When testosterone rises, whether from exogenous replacement or from endogenous stimulation, prostate cells can increase PSA secretion. This relationship is real but not linear. The "saturation model" of prostate androgen biology proposes that androgen receptors become fully occupied at relatively low testosterone concentrations (roughly 200-250 ng/dL), meaning that moving from low-normal to high-normal testosterone produces far less incremental PSA change than moving from castrate levels to low-normal. This model has important implications for how researchers interpret PSA data in enclomiphene studies.

Researchers exploring enclomiphene in male endocrine research and LH, FSH, and testosterone signaling need to understand this saturation dynamic before drawing conclusions from PSA fluctuations in study subjects.

Enclomiphene and PSA: What the Evidence Shows in 2026

Enclomiphene and PSA: What the Evidence Shows in 2026

Enclomiphene is the trans-isomer of clomiphene citrate. Unlike the mixed-isomer parent compound, it acts as a pure estrogen receptor antagonist at the hypothalamic-pituitary axis, blocking negative feedback and driving endogenous LH and FSH secretion, which in turn stimulates testicular testosterone production. This mechanism makes it conceptually distinct from exogenous testosterone, yet the downstream effect on prostate tissue is similar: higher circulating testosterone.

Phase III trials enrolling up to approximately 354 men over roughly six months have not shown a statistically significant PSA increase compared with placebo. No trial to date has demonstrated a cancer-incidence signal attributable to enclomiphene. Older comparative data pitting oral enclomiphene against transdermal testosterone gels found only small, clinically insignificant PSA changes with enclomiphene, changes that were not consistently observed with gels, suggesting that endogenous stimulation via a serm may affect PSA differently than direct exogenous androgen delivery.

For researchers building study designs, understanding how serms interact with polypeptide hormones in research provides essential context for interpreting hormone panels alongside PSA data.

Practical PSA Monitoring Thresholds

Current clinical guidance, updated through 2026, recommends the following framework for men receiving enclomiphene:

Checkpoint Action
Before starting (all men over 40) Obtain baseline PSA
Baseline PSA > 4.0 ng/mL Urology clearance before proceeding
Baseline PSA > 3.0 ng/mL + first-degree family history Urology clearance before proceeding
3-month recheck Compare with baseline; note velocity
6-month recheck Continue periodic monitoring
PSA rise > 1.4 ng/mL in any 3-12-month window Urology referral
PSA velocity > 0.75 ng/mL per year Urology referral

This framework mirrors Endocrine Society hypogonadism guidelines, which state that any testosterone-raising therapy, including enclomiphene, should be avoided in men with known prostate cancer, palpable nodules, or markedly elevated PSA at baseline.

GLP-Class Peptides and the PSA Interface: Where Research Stands

GLP-Class Peptides and the PSA Interface: Where Research Stands

GLP-1 receptor agonists and the newer triple-agonist GLP-3 class agents (such as retatrutide) have generated enormous research interest for their metabolic and cardiovascular effects. Researchers following GLP-3 retatrutide and triple-agonist peptide phase 3 obesity data will note that current endocrine and urology guidance does not integrate GLP-class agents into PSA-specific monitoring frameworks.

This absence is meaningful, not an oversight. GLP-1 and GLP-3 receptors are expressed in pancreatic beta cells, the gut, the brain, and cardiovascular tissue, but not in prostate epithelium at levels that would be expected to alter PSA transcription. These peptides work through cyclic AMP-mediated pathways that are mechanistically separate from the androgen receptor axis driving PSA production.

Where GLP-class research does intersect with prostate health indirectly:

  • Obesity is an established risk factor for aggressive prostate cancer; GLP-class agents that reduce visceral adiposity may theoretically reduce that background risk over time.
  • Weight loss lowers serum estrogen (produced in adipose tissue), which can slightly alter the testosterone-estrogen ratio, a variable that enclomiphene also modulates.
  • Researchers combining enclomiphene with GLP-class peptides in metabolic models, as explored in work on tesofensine, enclomiphene, and peptide-based approaches in metabolic research, should track PSA as part of a comprehensive safety panel even when GLP agents alone would not require it.

The key principle: PSA monitoring requirements are driven by the testosterone-raising component of any research protocol, not by the GLP-class peptide component.

Prostate Safety in Broader Hormone Research Contexts

Long-term observational data and multiple meta-analyses consistently show that testosterone replacement does not meaningfully accumulate in prostate tissue or provoke major biologic change beyond physiologic ranges. The American Urological Association permits carefully monitored testosterone therapy even in select men on active surveillance for low-risk prostate cancer, provided baseline and serial PSA plus imaging are tracked. This permissive but watchful stance extends logically to enclomiphene, which raises testosterone endogenously rather than exogenously.

Researchers working with growth hormone secretagogues alongside these agents can find relevant mechanistic background in the tesa and ipamorelin comparative analysis of growth hormone secretion mechanisms, as GH-axis peptides also affect body composition in ways that could influence the hormonal milieu relevant to PSA.

Conclusion

Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research comes down to one core principle: PSA is a downstream marker of androgen receptor activity in prostate tissue, and any compound that raises testosterone, directly or indirectly, warrants structured PSA surveillance. Enclomiphene raises endogenous testosterone and therefore fits within established monitoring protocols. GLP-class peptides, by contrast, operate through entirely different receptor pathways and carry no current evidence of PSA influence, though they may alter the broader hormonal environment when combined with serms.

Actionable steps for researchers and clinicians in 2026:

  1. Obtain a baseline PSA in all male subjects over 40 before initiating enclomiphene or any testosterone-raising protocol.
  2. Apply established velocity and threshold triggers (greater than 0.75 ng/mL per year; any single rise exceeding 1.4 ng/mL) to prompt urology evaluation.
  3. Do not apply PSA-specific monitoring requirements to GLP-class peptide protocols unless a testosterone-raising agent is co-administered.
  4. Document PSA alongside full hormone panels (LH, FSH, total and free testosterone) to distinguish therapy-driven changes from pathologic trends.
  5. Review the evolving literature on enclomiphene vs enclomiphene citrate formulation differences to ensure study compounds are correctly characterized before interpreting PSA data.

PSA monitoring is not a reason to avoid hormone-modulating research, it is the tool that makes that research safe and scientifically credible.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-and-hormone-modulating-compounds-how-psa-monitoring-in.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-12 13:12:172026-09-12 13:12:17Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research
GLP-2-T and GLP2 Tirz Peptides: Why Naming Matters for Translational Research and Trial Design

GLP-2-T and GLP2 Tirz Peptides: Why Naming Matters for Translational Research and Trial Design

August 16, 2026/0 Comments/in Uncategorized/by

A single mislabeled peptide in a vendor catalog can quietly derail months of preclinical work. As of 2026, the confusion surrounding GLP-2-T and GLP2 Tirz nomenclature has moved from a minor nuisance to a documented problem in translational research and trial design, one that experts are now actively working to resolve.

The core issue is straightforward but consequential: two structurally and mechanistically distinct compound classes are being sold, cited, and sometimes studied under overlapping names. Understanding why GLP-2-T and GLP2 Tirz peptides: why naming matters for translational research and trial design is not a semantic debate, it is a question of scientific integrity and patient safety.

Key Takeaways

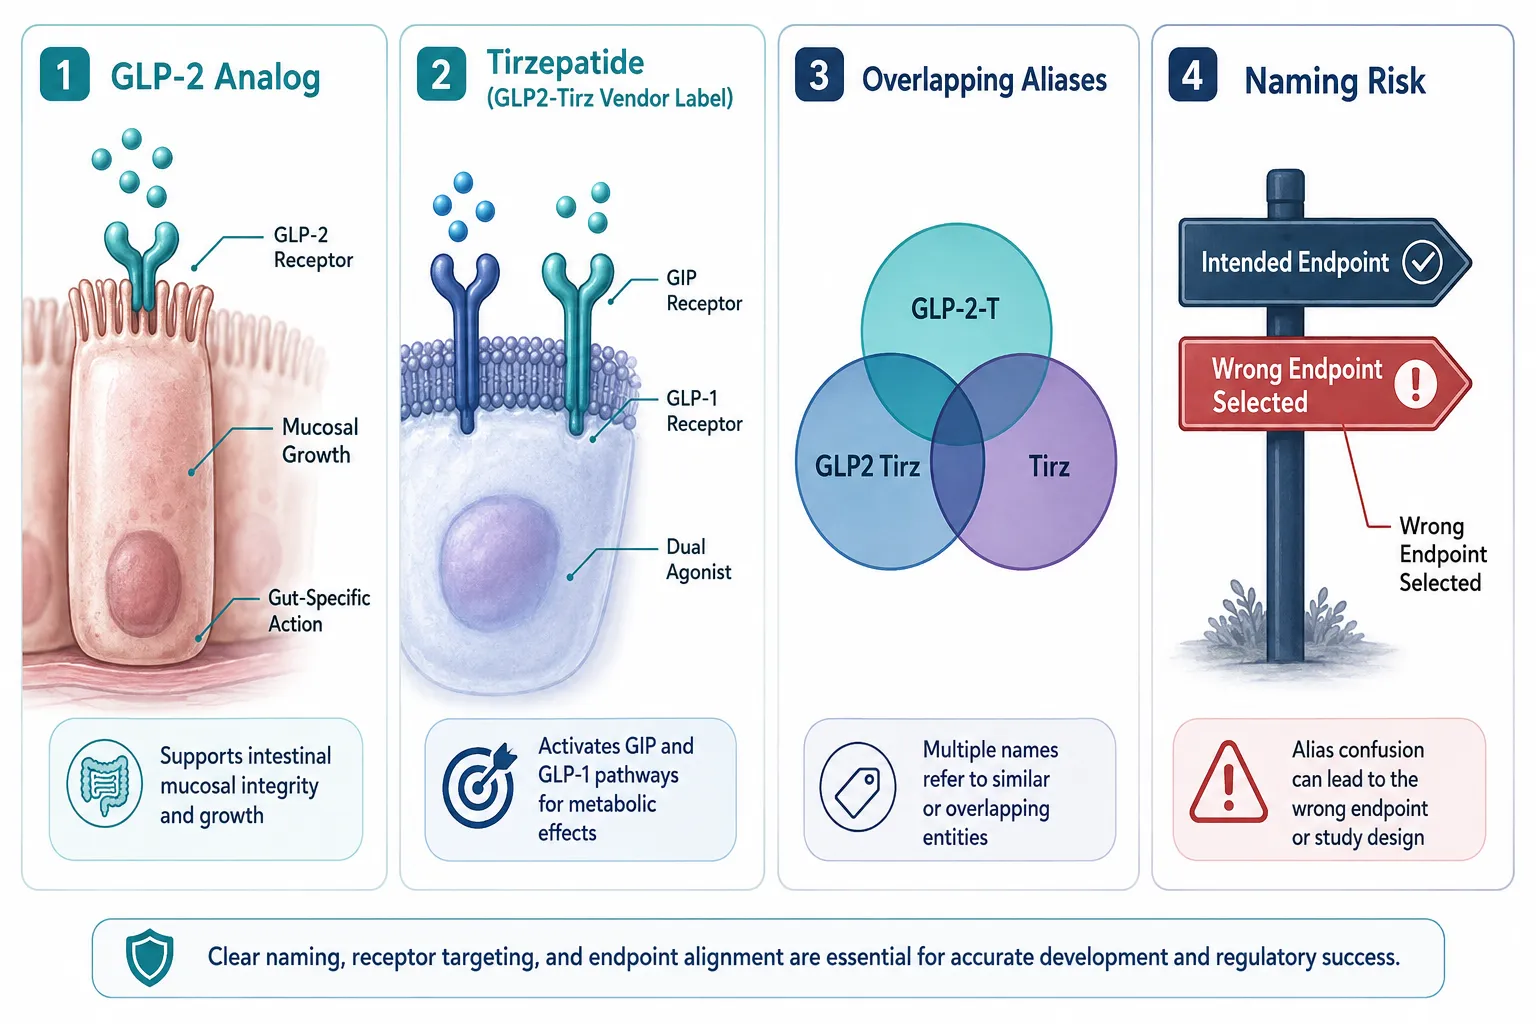
  • GLP-2 refers to a gut-specific peptide that acts on GLP-2 receptors to promote mucosal growth; GLP2 Tirz is a vendor alias increasingly applied to tirzepatide, a dual GIP/GLP-1 receptor agonist.
  • These two compound classes have entirely different receptor targets, mechanisms of action, and translational endpoints.
  • Vendor catalogs in 2026 show widespread aliasing of tirzepatide under GLP-2-adjacent labels, creating literature search contamination and protocol errors.
  • Experts recommend reverting to International Nonproprietary Names (INN) and explicit receptor labeling in all research documentation.
  • Early industry movement toward clearer disclosures is underway, but standardization is not yet complete.

Understanding the Two Compound Classes Behind the Naming Confusion

Understanding the Two Compound Classes Behind the Naming Confusion

GLP-2 (glucagon-like peptide-2) is a 33-amino-acid peptide secreted by intestinal L-cells. It binds selectively to the GLP-2 receptor, driving intestinal mucosal growth, reducing gut permeability, and supporting nutrient absorption. Analogs of GLP-2, such as teduglutide, are approved for short bowel syndrome and have a well-defined mechanistic profile tied entirely to gut biology.

Tirzepatide, on the other hand, is a dual agonist targeting both the GIP (glucose-dependent insulinotropic polypeptide) receptor and the GLP-1 receptor. It has no meaningful activity at the GLP-2 receptor. Its translational endpoints center on metabolic outcomes: glycemic control, body weight reduction, and insulin sensitivity. For researchers exploring GLP-1 peptides, tirzepatide represents a distinct pharmacological category from GLP-2 analogs.

The problem emerges in vendor catalogs and informal research communications. The shorthand "GLP2-T" or "GLP2 Tirz" has been applied to tirzepatide by multiple suppliers, likely because tirzepatide's name contains "tirz" and its GLP-class designation invites casual abbreviation. Meanwhile, mechanistic literature uses "GLP-2-T" to denote modified GLP-2 analogs. The result is a naming collision with real consequences.

Key distinction: GLP-2 analogs act on the gut epithelium. Tirzepatide acts on pancreatic and hypothalamic GIP/GLP-1 receptors. Conflating these in a protocol is not a minor error, it is a fundamental mechanistic mismatch.

How Naming Errors Enter Research Protocols and Trial Design

How Naming Errors Enter Research Protocols and Trial Design

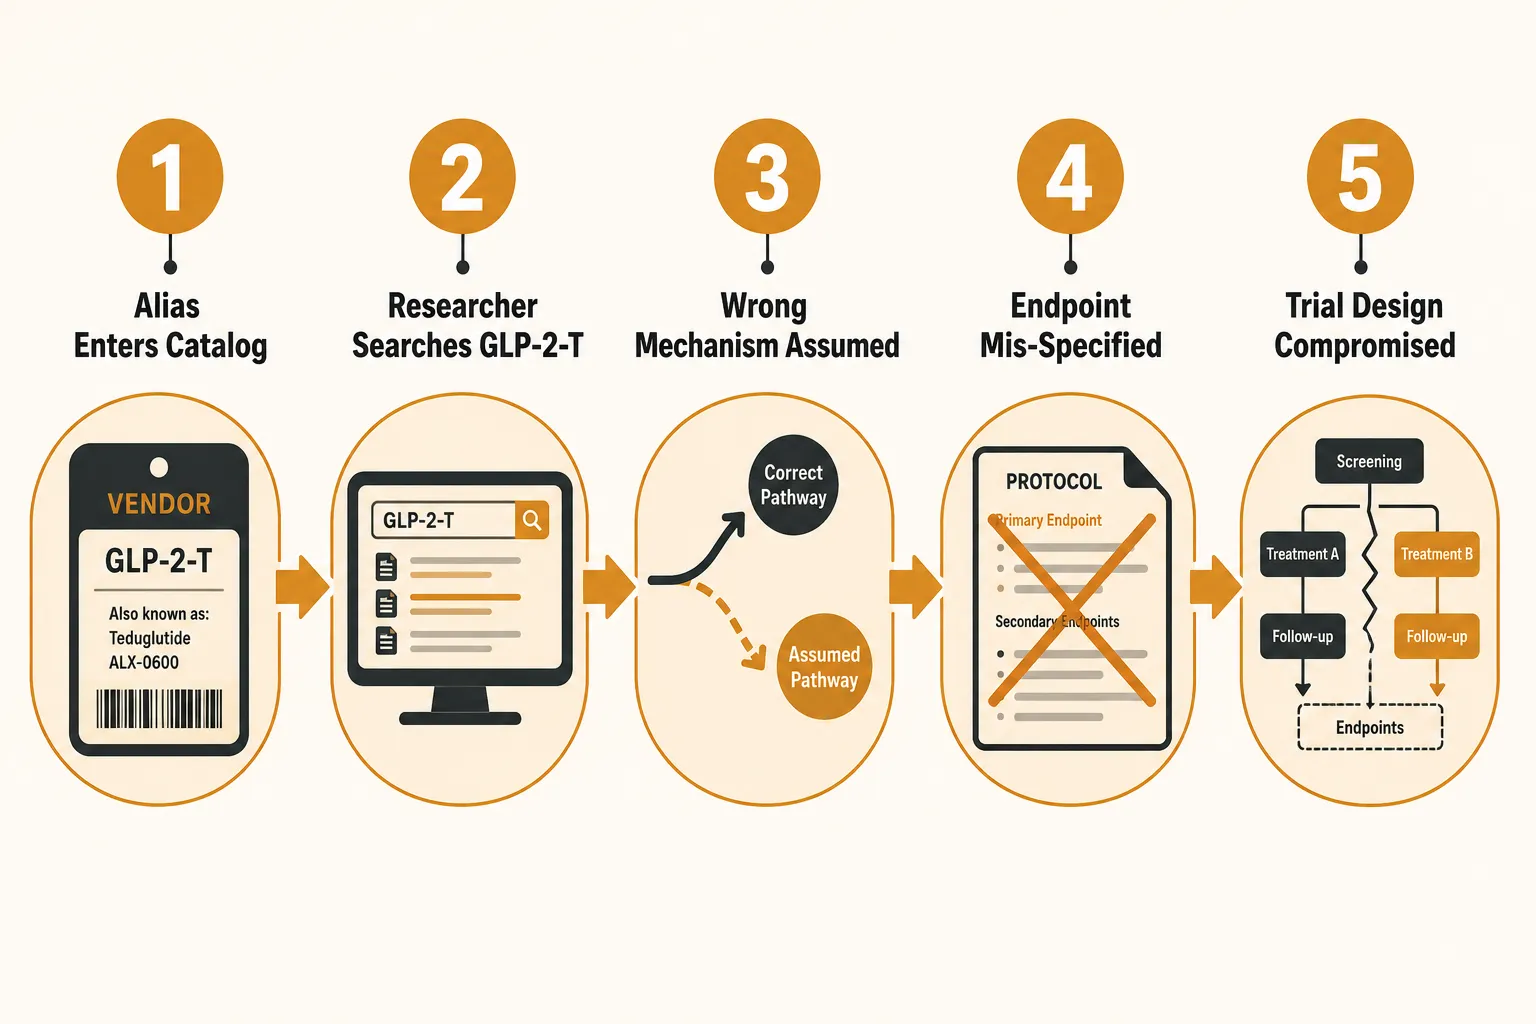
The pathway from naming confusion to flawed trial design follows a predictable sequence. A researcher queries a database or vendor catalog using "GLP-2-T." They retrieve results that include both genuine GLP-2 analog literature and tirzepatide vendor listings. Without careful cross-referencing of CAS numbers or INN designations, the wrong compound profile gets incorporated into a protocol.

This matters most at three points in research design:

1. Endpoint selection
GLP-2 analog studies measure intestinal villus height, crypt depth, tight junction protein expression, and gut permeability markers. Tirzepatide studies measure HbA1c, body mass index, fasting glucose, and lipid panels. A protocol built on the wrong compound assumption will specify endpoints that cannot detect the actual mechanism at work.

2. Inclusion and exclusion criteria
Subjects enrolled for a GLP-2 mechanism study, for example, patients with inflammatory bowel conditions or short bowel syndrome, are categorically different from subjects appropriate for a tirzepatide metabolic study. Naming errors upstream can produce inclusion criteria that are scientifically incoherent.

3. Literature search contamination
Systematic reviews and meta-analyses depend on clean search terms. When "GLP2-T" retrieves a mix of GLP-2 analog and tirzepatide studies, pooled analyses become unreliable. This is not a hypothetical risk, it is an active problem flagged by researchers in 2026.

Researchers working with related GLP-class compounds, including those exploring GLP-1 Tirz 60mg GA2 formulations, should verify receptor specificity before drawing mechanistic parallels. Similarly, those following retatrutide Phase 3 and beyond developments will recognize that multi-receptor agonist nomenclature is already complex enough without additional aliasing.

Expert Recommendations and the Path Toward Standardization

Expert Recommendations and the Path Toward Standardization

The expert consensus emerging in 2026 is clear: all research documentation, vendor communications, and trial protocols should use INN designations (tirzepatide, teduglutide) and explicit receptor labels (GIP/GLP-1 dual agonist; GLP-2 receptor agonist) rather than shorthand aliases.

Specific recommendations include:

  • Always cross-reference CAS numbers when sourcing peptides from vendor catalogs, particularly for GLP2-T tagged products where alias use is documented.
  • State receptor targets explicitly in Methods sections, "dual GIP/GLP-1 receptor agonist (tirzepatide)" rather than "GLP2 Tirz."
  • Audit literature search strings in systematic reviews to exclude alias contamination before pooling data.
  • Request certificates of analysis that include INN and CAS number, not just catalog shorthand.

Some vendors are beginning to add clarifying disclosures to listings, a positive early sign. However, marketplace data from mid-2026 shows that alias use remains widespread across supplier catalogs, meaning researchers cannot yet rely on vendor labeling alone.

The broader principle applies across peptide research categories. Nomenclature discipline is equally important in adjacent fields, researchers working with compounds like those covered in BPC-157 TB-500 peptide research or BDNF peptides understand that precise naming underpins reproducible science.

For those sourcing research-grade GLP-class compounds, oral peptides for sale resources that include full INN disclosure represent the current best practice standard.

Conclusion

The confusion surrounding GLP-2-T and GLP2 Tirz peptides: why naming matters for translational research and trial design is a concrete, solvable problem, but only if researchers, vendors, and trial designers treat it as a priority rather than a footnote.

Actionable next steps for researchers and trial designers:

  1. Verify every GLP-class compound against its INN and CAS number before incorporating it into a protocol.
  2. Rewrite any Methods section that uses "GLP2-T" or "GLP2 Tirz" without explicit receptor designation.
  3. Audit systematic review search strings for alias contamination before finalizing inclusion criteria.
  4. Advocate for vendor disclosure standards that require INN labeling alongside catalog shorthand.
  5. Treat mechanistic divergence, gut epithelial vs. metabolic receptor targets, as a hard boundary when selecting translational endpoints.

Standardization is coming, but it is not here yet. Until it is, the responsibility falls on individual researchers to close the gap between what a label says and what a compound does.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/glp-2-t-and-glp2-tirz-peptides-why-naming-matters-for-translational-research-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-16 13:04:022026-08-16 13:04:02GLP-2-T and GLP2 Tirz Peptides: Why Naming Matters for Translational Research and Trial Design
Peptide Calculators in Research: How Labs Estimate Dosing, Concentration, and Reconstitution

Peptide Calculators in Research: How Labs Estimate Dosing, Concentration, and Reconstitution

August 15, 2026/0 Comments/in Uncategorized/by

A single miscalculation in peptide reconstitution can render an entire experiment invalid, yet the math behind it is straightforward once researchers understand the core formulas. Peptide calculators in research: how labs estimate dosing, concentration, and reconstitution has become a central workflow topic in 2026, with multiple platforms releasing or updating dedicated calculation tools to support bench scientists working with compounds such as CJC-1295, Tesamorelin, and GLP-class molecules. This article is a technical tutorial for research use only, covering the underlying math, practical workflows, and common error-checking steps that modern peptide calculators are built around.

Key Takeaways

  • The core concentration formula is: Concentration (mg/mL) = Vial Mass (mg) / Diluent Volume (mL)
  • Converting between mg and mcg (1 mg = 1,000 mcg) is the most common source of calculation error
  • U-100 insulin syringes require an additional unit conversion: 1 IU = 0.01 mL
  • Modern peptide calculators use 3-4 step workflows and include error-checking to validate syringe capacity
  • All calculations assume uniform dissolution of the peptide in bacteriostatic water

The Core Math Behind Peptide Concentration Calculations

The Core Math Behind Peptide Concentration Calculations

Every peptide calculator in research begins with one foundational equation. Once a lyophilized peptide is reconstituted in bacteriostatic water (BW), the resulting solution is assumed to be uniformly dissolved throughout the vial. This assumption makes the concentration formula clean and reliable:

Concentration (mg/mL) = Vial Mass (mg) / Reconstitution Volume (mL)

For example, a 5 mg vial of CJC-1295 reconstituted with 2.5 mL of bacteriostatic water yields a concentration of 2 mg/mL. If a researcher needs outputs in micrograms per milliliter, common in cell culture and assay protocols, the formula adjusts:

Concentration (mcg/mL) = (Vial Mass in mg × 1,000) / Diluent Volume (mL)

Using the same example: (5 × 1,000) / 2.5 = 2,000 mcg/mL.

The relationship 1 mg = 1,000 mcg is highlighted repeatedly in calculator documentation because it is the most frequent source of dosing errors. Researchers working with compounds like Tesamorelin and Ipamorelin combination protocols must pay particular attention to this conversion, as both compounds are often dosed in the low-microgram range.

Deriving Injection Volume from Concentration

Once concentration is established, the draw volume for a target dose follows directly:

Draw Volume (mL) = Target Dose (mg or mcg) / Concentration (mg/mL or mcg/mL)

If the target research dose is 1 mg and the concentration is 2 mg/mL, the draw volume is 0.5 mL. This simple division is the backbone of every peptide dosing calculator available in 2026.

Syringe Unit Conversion: Translating mL Into IU on a U-100 Scale

Syringe Unit Conversion: Translating mL Into IU on a U-100 Scale

Most research labs use U-100 insulin syringes for subcutaneous peptide administration in animal models. These syringes are calibrated in International Units (IU), not milliliters, which introduces a conversion step that peptide calculators in research consistently address.

The key relationship is:

Measurement Equivalent
1 mL 100 IU
1 IU 0.01 mL
0.5 mL 50 IU
0.1 mL 10 IU

To convert a draw volume in mL to syringe units:

Syringe Units (IU) = Draw Volume (mL) × 100

Using the earlier example: 0.5 mL × 100 = 50 IU on the syringe scale.

Modern calculators present this as part of a guided 4-step workflow:

  1. Enter vial mass (mg)
  2. Enter bacteriostatic water volume (mL)
  3. Enter target dose (mg or mcg)
  4. Receive draw volume in mL and IU

Some tools include visual syringe meters that animate exactly where to stop drawing on the scale, a practical feature for labs running high-throughput assays with compounds like those explored in SS-31 mechanism and research.

Error-Checking and Capacity Validation

A notable feature in 2026 calculator updates is capacity validation, the tool checks whether the calculated draw volume exceeds the selected syringe's maximum capacity. If a researcher selects a 0.3 mL syringe but the calculation returns 0.45 mL, the calculator flags the mismatch before any solution is drawn. Back-check logic also allows users to confirm that concentration, dose, and syringe units are internally consistent, reducing the risk of compounding errors across multi-compound protocols.

Applying Peptide Calculators to GLP-Class and Advanced Research Compounds

Applying Peptide Calculators to GLP-Class and Advanced Research Compounds

The same mg/mL concentration logic that governs classic research peptides applies directly to GLP-1 agonists, GLP-3 class molecules, and adjunct compounds like NAD+. This consistency has driven broad adoption of standardized peptide calculators across metabolic and longevity research programs.

For a GLP-class compound supplied as a 10 mg vial, reconstituted with 5 mL of bacteriostatic water:

  • Concentration = 10 / 5 = 2 mg/mL (or 2,000 mcg/mL)
  • Target dose of 0.5 mg = draw volume of 0.25 mL (25 IU on a U-100 syringe)

Researchers studying compounds such as those reviewed in Selank peptide research benefits and dosing concepts or MOTS-c mitochondrial signaling and metabolic research apply identical formulas, adjusting only the vial mass and target dose inputs.

For in-vitro protocols, such as cell culture or enzyme assays, calculators offer fields labeled "research amount" and "volume of reconstituted solution used in your experiment," returning outputs in mg/mL, mcg/mL, and IU. This makes the same tool useful across both in-vivo animal model work and bench-based assay preparation.

"The uniformity assumption, that a reconstituted peptide is evenly dissolved throughout the vial, is what makes the mg/mL formula reliable and repeatable across research contexts."

Labs sourcing compounds like GHK-Cu copper peptides or PT-141 in research context QA and controls benefit from pairing supplier documentation with a validated calculator workflow to ensure concentration consistency across experimental batches.

Quick Reference: Common Reconstitution Scenarios

Vial Size BW Added Concentration 0.5 mg Dose Draw
2 mg 1 mL 2 mg/mL 0.25 mL / 25 IU
5 mg 2.5 mL 2 mg/mL 0.25 mL / 25 IU
10 mg 5 mL 2 mg/mL 0.25 mL / 25 IU
5 mg 5 mL 1 mg/mL 0.5 mL / 50 IU

Conclusion

Peptide calculators in research: how labs estimate dosing, concentration, and reconstitution comes down to three sequential calculations, concentration from vial mass and diluent volume, draw volume from concentration and target dose, and syringe units from draw volume and the U-100 scale. The math is accessible, but the consequences of skipping steps or mishandling unit conversions are significant in a research context.

Actionable next steps for research teams:

  • Standardize on a single reconstitution volume per compound to keep concentration consistent across experimental runs
  • Always verify the mg-to-mcg conversion before entering values into any calculator
  • Use a calculator with capacity validation to confirm syringe selection before drawing
  • Document concentration, draw volume, and IU for every batch in the lab notebook
  • Cross-reference calculator outputs against the underlying formula manually at least once per new compound

For labs working with a broad compound library, pairing a validated peptide calculator with high-purity, lab-tested peptides and reliable supplier documentation is the most effective way to maintain experimental integrity across studies.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/peptide-calculators-in-research-how-labs-estimate-dosing-concentration-and-recon.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-15 13:04:532026-08-15 13:04:53Peptide Calculators in Research: How Labs Estimate Dosing, Concentration, and Reconstitution
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top