Retatrutide Mechanism Explained: How GIP, GLP-1, and Glucagon Signaling Differ From Single-Incretin Models
Obesity drug development spent decades chasing a single receptor. Retatrutide broke that convention by engaging three simultaneously, and the metabolic consequences are not simply additive. Understanding the retatrutide mechanism explained through its GIP, GLP-1, and glucagon signaling offers a clearer picture of why this triple-agonist behaves so differently from earlier single-incretin models and why its clinical results have drawn serious scientific attention in 2026.
Key Takeaways
- Retatrutide activates GIP, GLP-1, and glucagon receptors through a shared Gs-cAMP-PKA signaling cascade, but each receptor produces distinct downstream tissue effects.
- The glucagon arm is the primary differentiator from dual-agonist drugs like tirzepatide, driving thermogenesis and hepatic fat clearance beyond what incretin signaling alone can achieve.
- Triple-receptor engagement produces synergistic, not merely additive, metabolic effects across the pancreas, brain, adipose tissue, and liver.
- Phase 2 clinical data show weight loss approaching bariatric surgery benchmarks, a threshold no approved single-incretin drug has reached.
- The tolerability profile is broadly comparable to GLP-1 analogues, though the glucagon arm requires careful dose calibration to avoid hyperglycemia risk.
The Shared Signaling Foundation: Gs-cAMP-PKA Across All Three Receptors
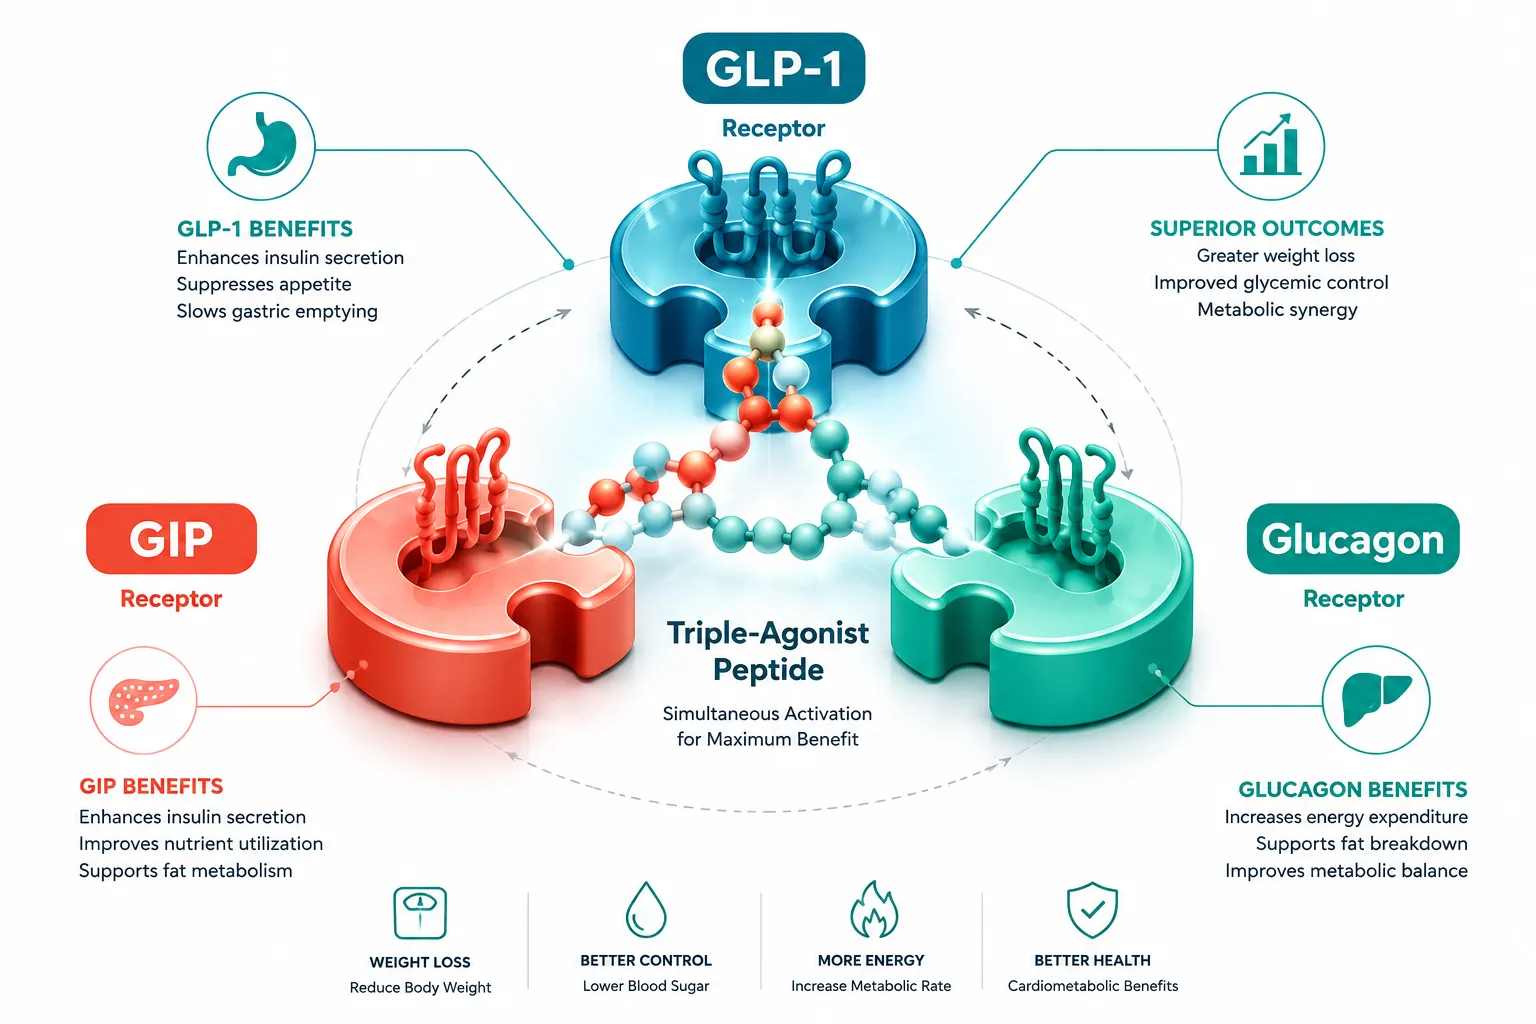
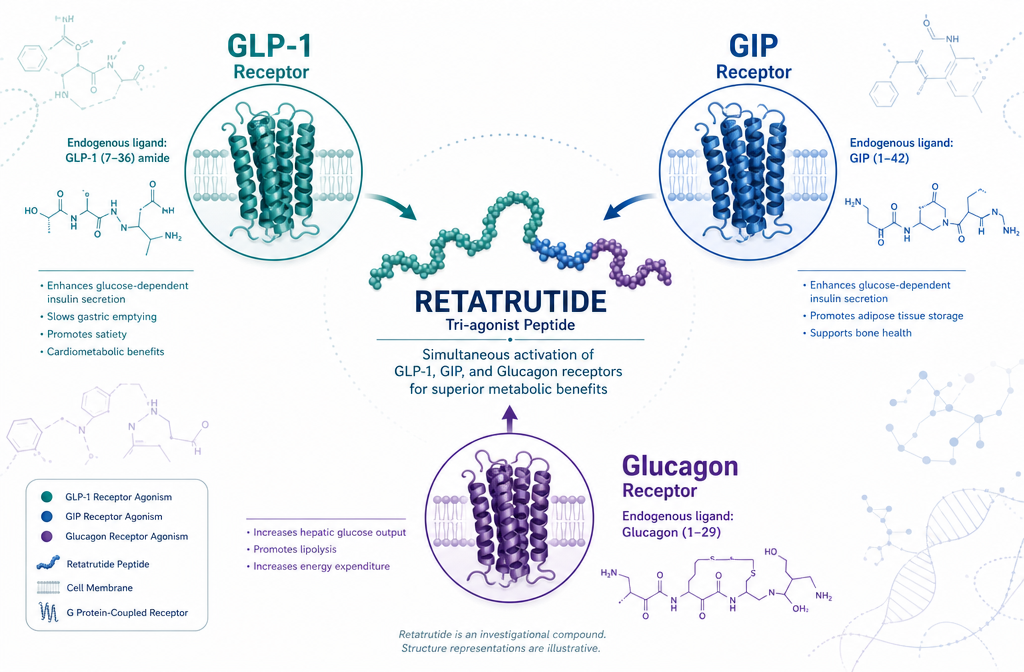
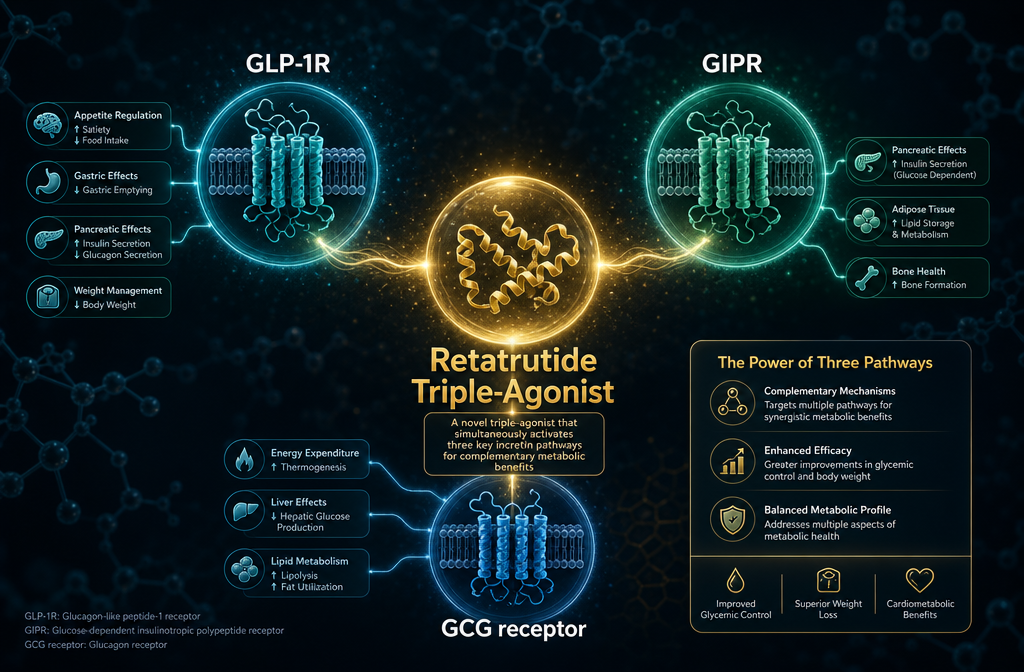
All three receptors targeted by retatrutide, the GIP receptor (GIPR), the GLP-1 receptor (GLP-1R), and the glucagon receptor (GCGR), belong to the class B G-protein-coupled receptor (GPCR) family. When retatrutide binds any of them, it activates the stimulatory G-protein (Gs), which triggers adenylyl cyclase to produce cyclic AMP (cAMP). Rising cAMP activates protein kinase A (PKA), initiating downstream transcription and cellular responses.
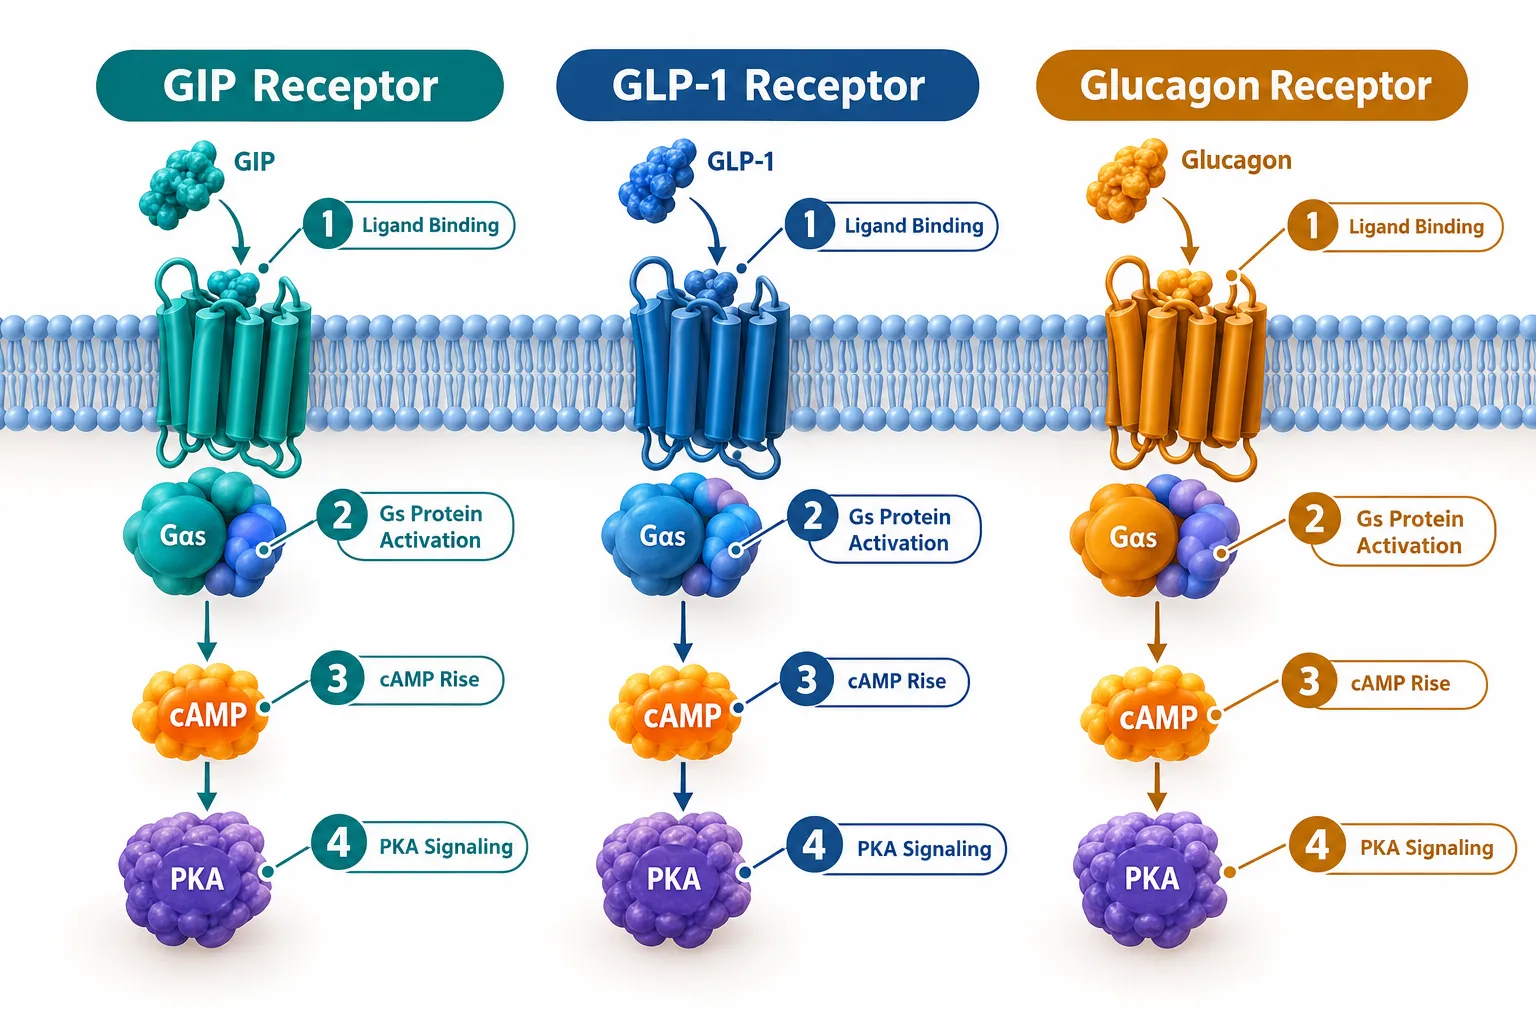
This shared architecture is important because it means retatrutide does not need to operate through fundamentally different biochemical languages at each receptor. What differs is the tissue distribution of each receptor and the physiological programs those receptors control once PKA is activated.
"The molecular key is the same; what changes is which door it opens, and in which organ."
- GIPR is expressed heavily in adipose tissue, bone, and the gut, with moderate pancreatic beta-cell presence.
- GLP-1R is concentrated in pancreatic beta cells, the hypothalamus, the brainstem, and the stomach.
- GCGR is dominant in the liver, adipose tissue, and the heart, with a smaller presence in the brain.
This tissue map is the first reason why a triple-agonist produces effects that a single-incretin model simply cannot replicate.
How the Three Receptor Arms Differ: A Retatrutide Mechanism Explained Comparison
GLP-1 Receptor Signaling: The Established Anchor
GLP-1R activation is the best-understood arm. In the pancreas, it amplifies glucose-dependent insulin secretion and suppresses glucagon release from alpha cells. In the hypothalamus and brainstem, GLP-1R signaling reduces appetite and slows gastric emptying. These effects underpin the entire class of GLP-1 analogues, semaglutide, liraglutide, and they are fully preserved in retatrutide.
Explore the broader landscape of GLP-1 Reta research to understand how this receptor arm is positioned within the compound's overall profile.
GIP Receptor Signaling: The Tolerability and Fat-Tissue Modifier
GIPR activation was historically undervalued because early GIP-only studies produced modest glycemic effects. The dual-agonist tirzepatide changed that perspective by showing that GIPR co-activation potentiates GLP-1R signaling and improves tolerability, likely by reducing nausea through central mechanisms.
In adipose tissue, GIPR activation promotes lipid uptake and storage in a way that, paradoxically, appears to support fat redistribution rather than simple fat accumulation when combined with the energy-expenditure signals from the glucagon arm. GIPR also has roles in bone turnover and may influence the gut microbiome, though these remain active research questions.
Glucagon Receptor Signaling: The Differentiating Engine
The GCGR arm is what most sharply separates retatrutide from all approved single-incretin and dual-incretin drugs. Glucagon is classically viewed as a counter-regulatory hormone that raises blood glucose, which is exactly why adding glucagon agonism to an obesity drug seems counterintuitive at first.
The resolution lies in context and dose calibration. At the modest glucagon receptor activity built into retatrutide's design, the dominant effects are:
- Hepatic fat mobilization, GCGR activation in the liver promotes fatty acid oxidation and reduces hepatic lipid accumulation, making retatrutide particularly relevant for metabolic-associated steatotic liver disease (MASLD).
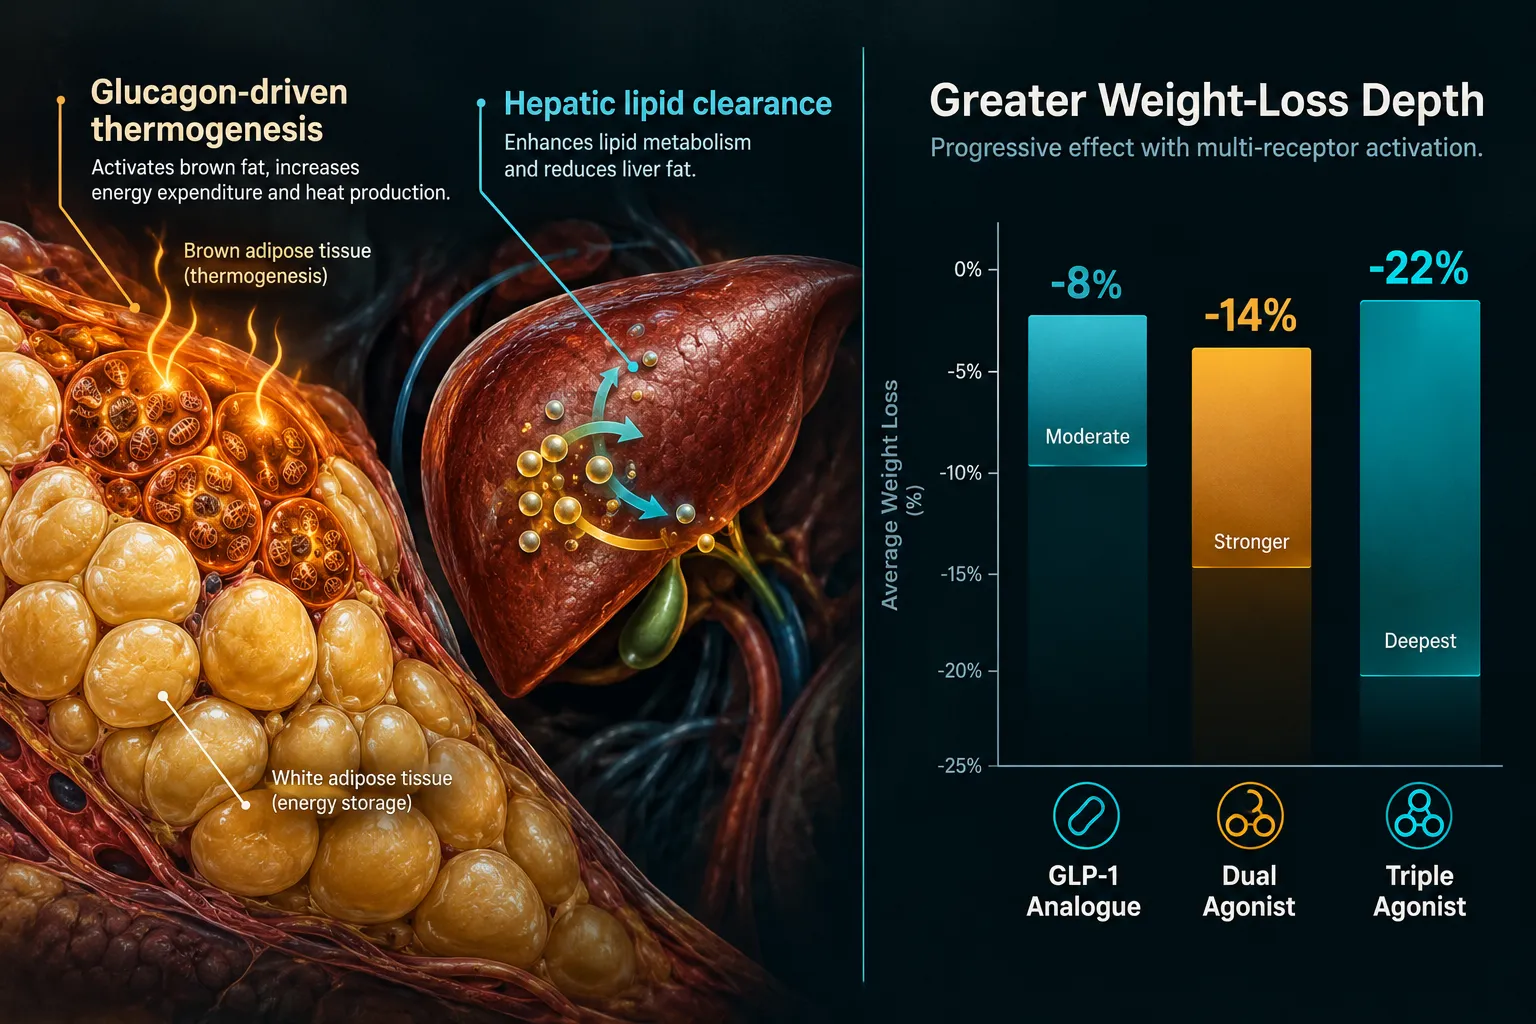
- Thermogenesis, Glucagon signaling in brown adipose tissue and the liver increases basal energy expenditure, a mechanism absent from GLP-1-only models.
- Satiety reinforcement, Central GCGR signaling in the hypothalamus contributes an additional appetite-suppressing signal independent of GLP-1R.
The glycemic risk from glucagon agonism is counterbalanced by the simultaneous GLP-1R-driven insulin secretion. This built-in counterweight is a deliberate pharmacological feature, not a coincidence.
Triple-Receptor Synergy vs. Single-Incretin Models: Why the Math Is Not Additive
The most important conceptual shift in understanding the retatrutide mechanism is recognizing that the three arms interact, not merely coexist.
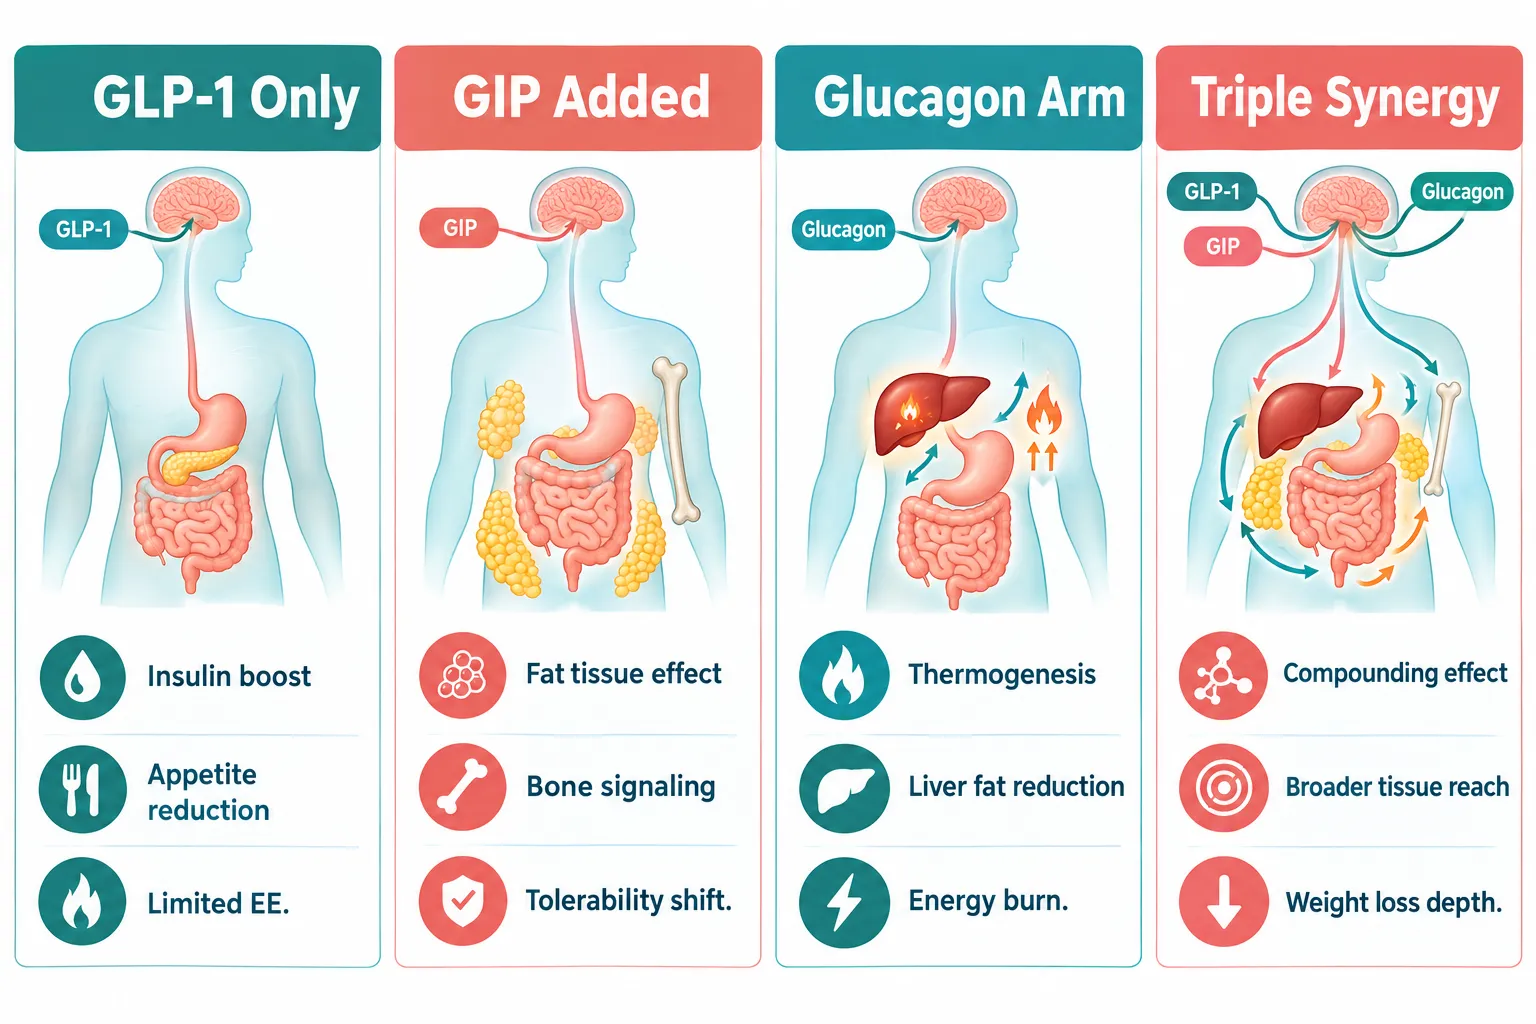
| Mechanism | GLP-1 Analogue | Dual Agonist (GIP+GLP-1) | Retatrutide (Triple) |
|---|---|---|---|
| Insulin secretion | Strong | Strong | Strong |
| Appetite suppression | Strong | Strong | Strong |
| Adipose tissue signaling | Indirect | Direct (GIPR) | Direct (GIPR) |
| Hepatic fat clearance | Modest | Modest | Significant (GCGR) |
| Thermogenesis / EE | Minimal | Minimal | Meaningful (GCGR) |
| Tolerability support | Baseline | Improved | Comparable to dual |
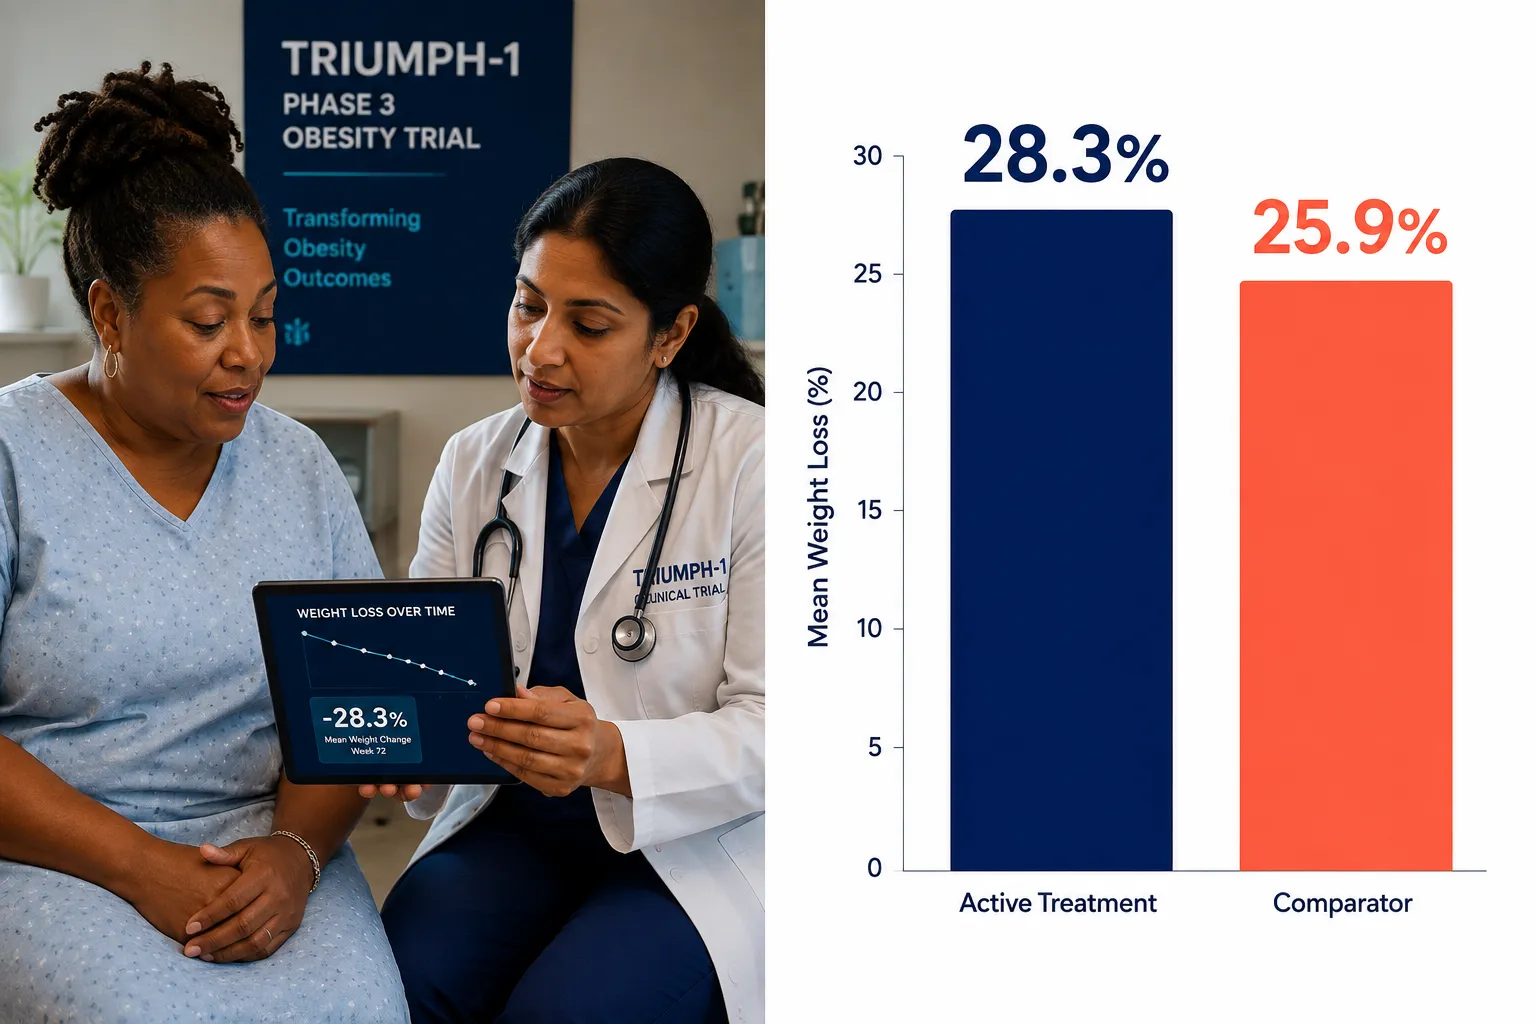
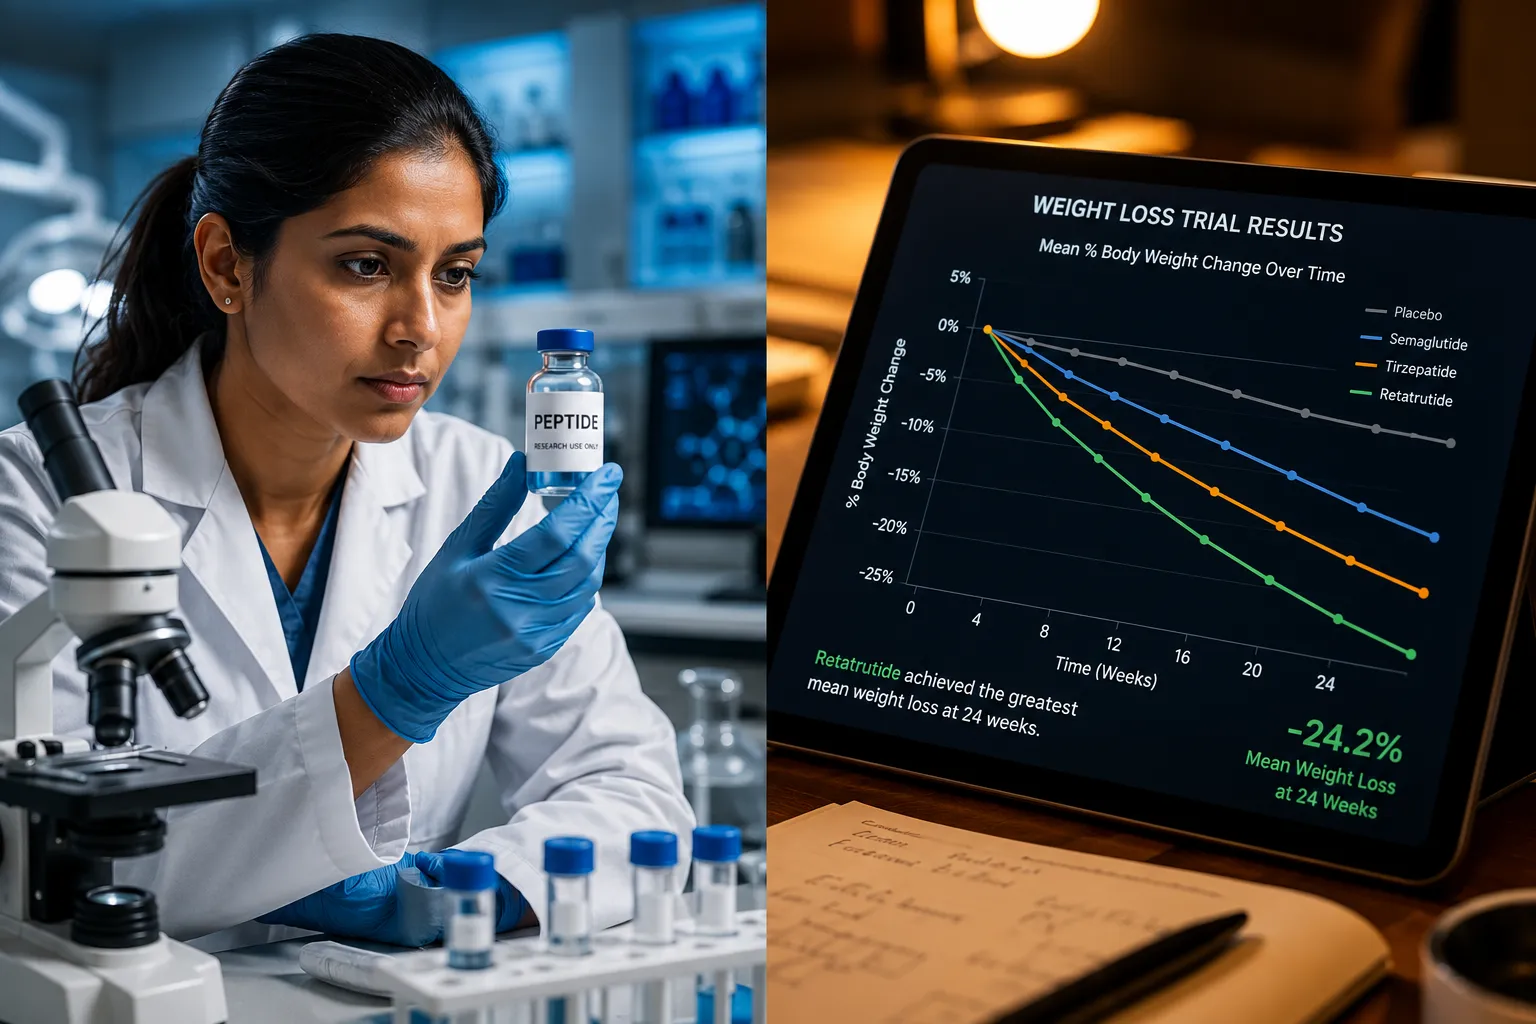
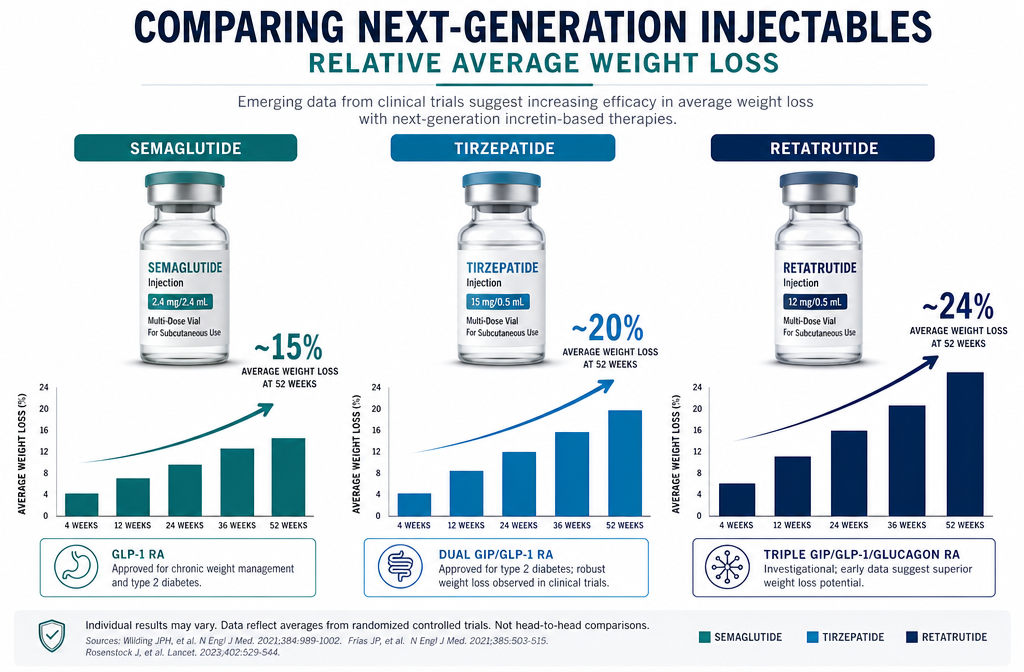
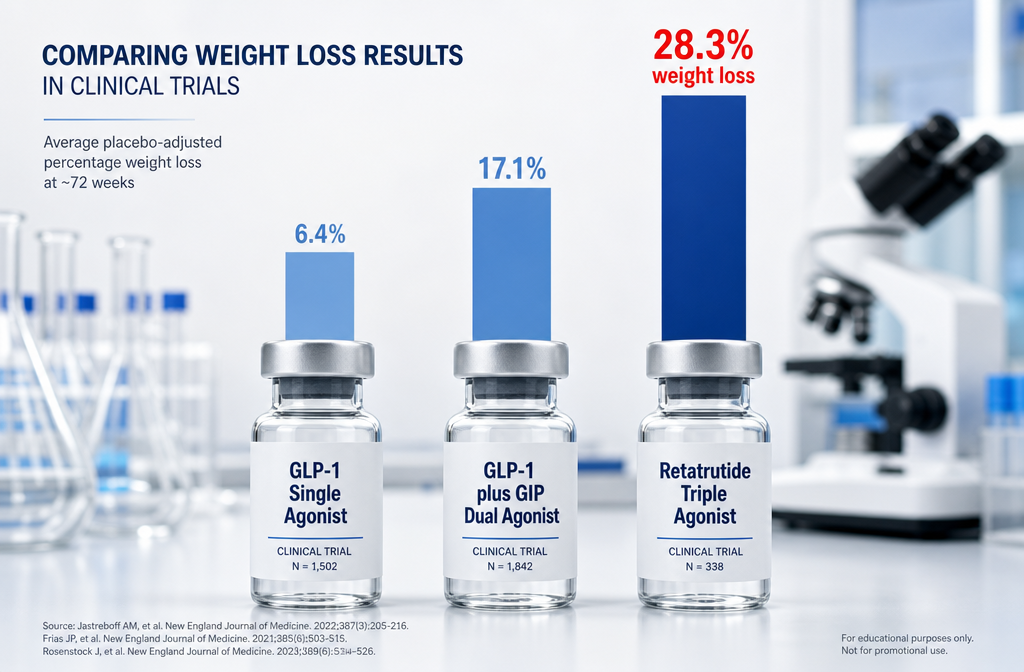
This multi-lever action explains why phase 2 trial data for retatrutide have shown mean weight reductions exceeding 24% of body weight at the highest doses over 48 weeks, figures that approach outcomes historically associated with bariatric surgery. Researchers following Retatrutide clinical trials can track how these mechanistic predictions have translated into human outcomes.
For a useful contrast with non-incretin appetite modulation, the Tesofensine mechanism explained article outlines how noradrenergic pathways differ from this receptor-based approach.
Safety Profile, Open Questions, and the Road Ahead
Retatrutide's tolerability profile in trials has been broadly consistent with the GLP-1 drug class: nausea, vomiting, and diarrhea are the most common adverse events, predominantly dose-dependent and transient. The glucagon arm has not produced clinically significant hyperglycemia in non-diabetic participants, validating the pharmacological counterbalance design. Lean mass preservation remains an area of ongoing investigation, as with all potent weight-loss agents.
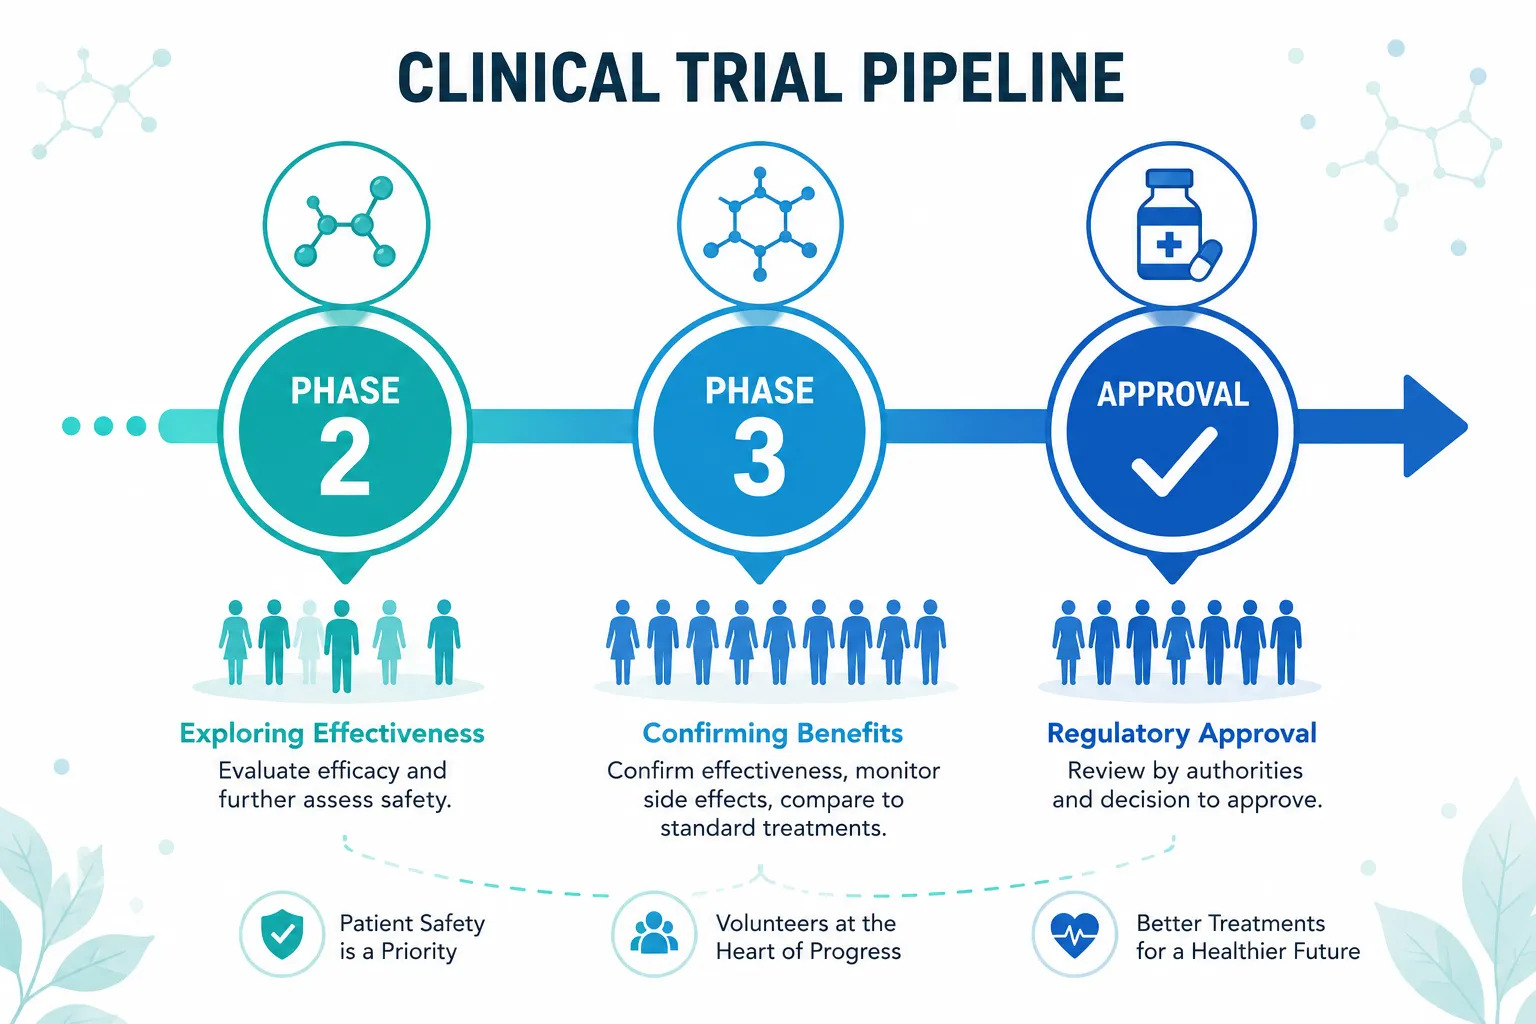
As of late 2026, retatrutide remains in late-stage clinical development and has not received regulatory approval in any major market. Phase 3 cardiovascular outcomes data are awaited, and the compound's long-term effects on bone density, given the GIPR's known skeletal role, are still being characterized.
Research-grade material is available for preclinical investigation. Those sourcing it can review options such as Reta 20mg for sale or browse the GLP Reta product category for available formats.
The broader industry is already exploring next-generation molecules that add a fourth receptor target, such as amylin or FGF21, to the triple-agonist scaffold, suggesting that retatrutide may represent a transitional rather than terminal point in metabolic pharmacology.
Conclusion
The retatrutide mechanism explained through its GIP, GLP-1, and glucagon signaling reveals a compound that is architecturally distinct from single-incretin models in three concrete ways: it adds a direct adipose-tissue signal via GIPR, it introduces a thermogenic and hepatic fat-clearing engine via GCGR, and it produces synergistic cross-receptor effects that no single or dual-incretin drug can replicate. For researchers and clinicians tracking this space, the actionable next steps are clear:
- Follow phase 3 data closely, particularly cardiovascular outcomes and lean mass metrics, as these will determine the real-world risk-benefit profile.
- Distinguish mechanism from marketing, the glucagon arm is the true differentiator; any future triple-agonist without it is functionally a dual-incretin drug.
- Monitor regulatory timelines across the US, EU, and key Asian markets, where approval decisions could arrive within the next 12 to 24 months.
- Engage with preclinical research responsibly, using verified, research-grade material from reputable sources when conducting laboratory investigations.
The triple-receptor model has redefined what metabolic pharmacology can achieve. Understanding the mechanism is the foundation for evaluating everything that follows.