Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: growth hormone secretagogues

Amlodipine, Metoprolol, and Losartan in Peptide Experiments: Choosing Cardiovascular Control Arms

Amlodipine, Metoprolol, and Losartan in Peptide Experiments: Choosing Cardiovascular Control Arms

October 21, 2026/0 Comments/in Uncategorized/by

Fewer than one in five published peptide cardiovascular studies include a mechanistically matched small-molecule control arm, a gap that makes it nearly impossible to separate a peptide's novel activity from effects shared with established drugs. For researchers working with retatrutide, growth-hormone secretagogues, natriuretic peptides, or any vascular-active compound, the choice between amlodipine, metoprolol, and losartan in peptide experiments is not a formality. It is a core design decision that determines whether the data can actually answer a mechanistic question.

Key Takeaways

  • Amlodipine, metoprolol, and losartan target three distinct cardiovascular axes, calcium influx, beta-adrenergic signaling, and RAAS, so the right control depends entirely on the peptide's suspected pathway.
  • Mismatching a control drug to a peptide target confounds results; a beta-blocker control is irrelevant in a calcium-handling study.
  • Standard in vitro concentration ranges for these agents are well-established and should bracket the peptide's tested range.
  • Shared readouts (force of contraction, cAMP levels, BNP secretion) allow direct comparison between drug controls and peptide effects.
  • Building rigorous reference benchmarks around control arms strengthens the experimental framework for any cardiovascular peptide study.

Why Mechanistic Matching Is the First Rule
Why Mechanistic Matching Is the First Rule

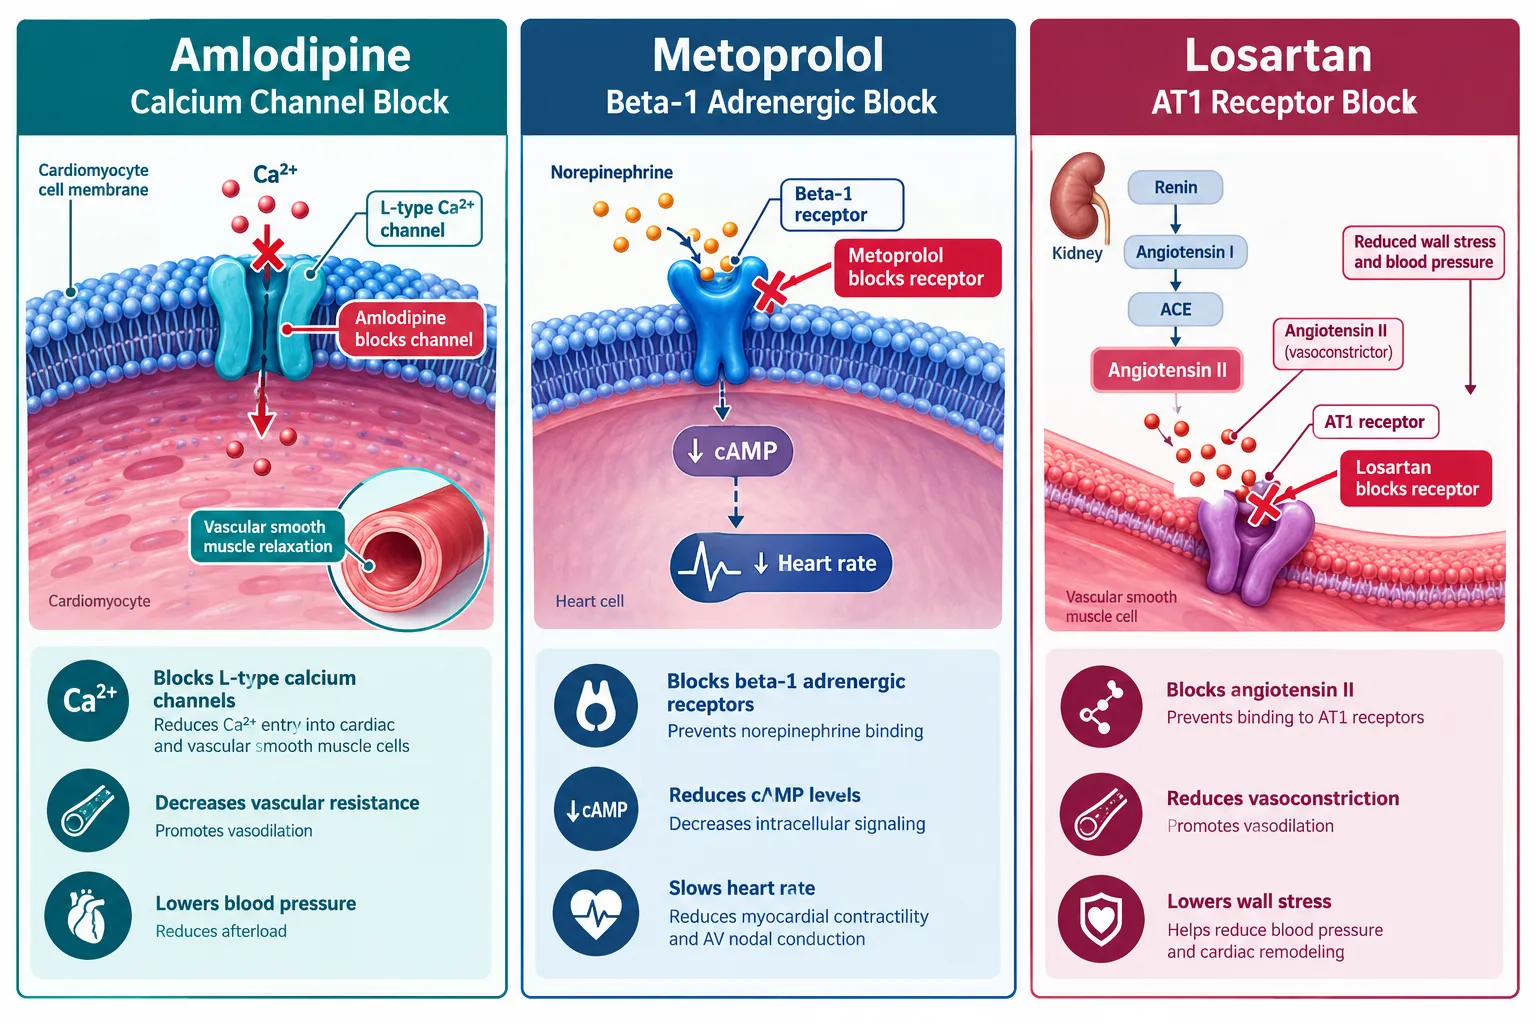
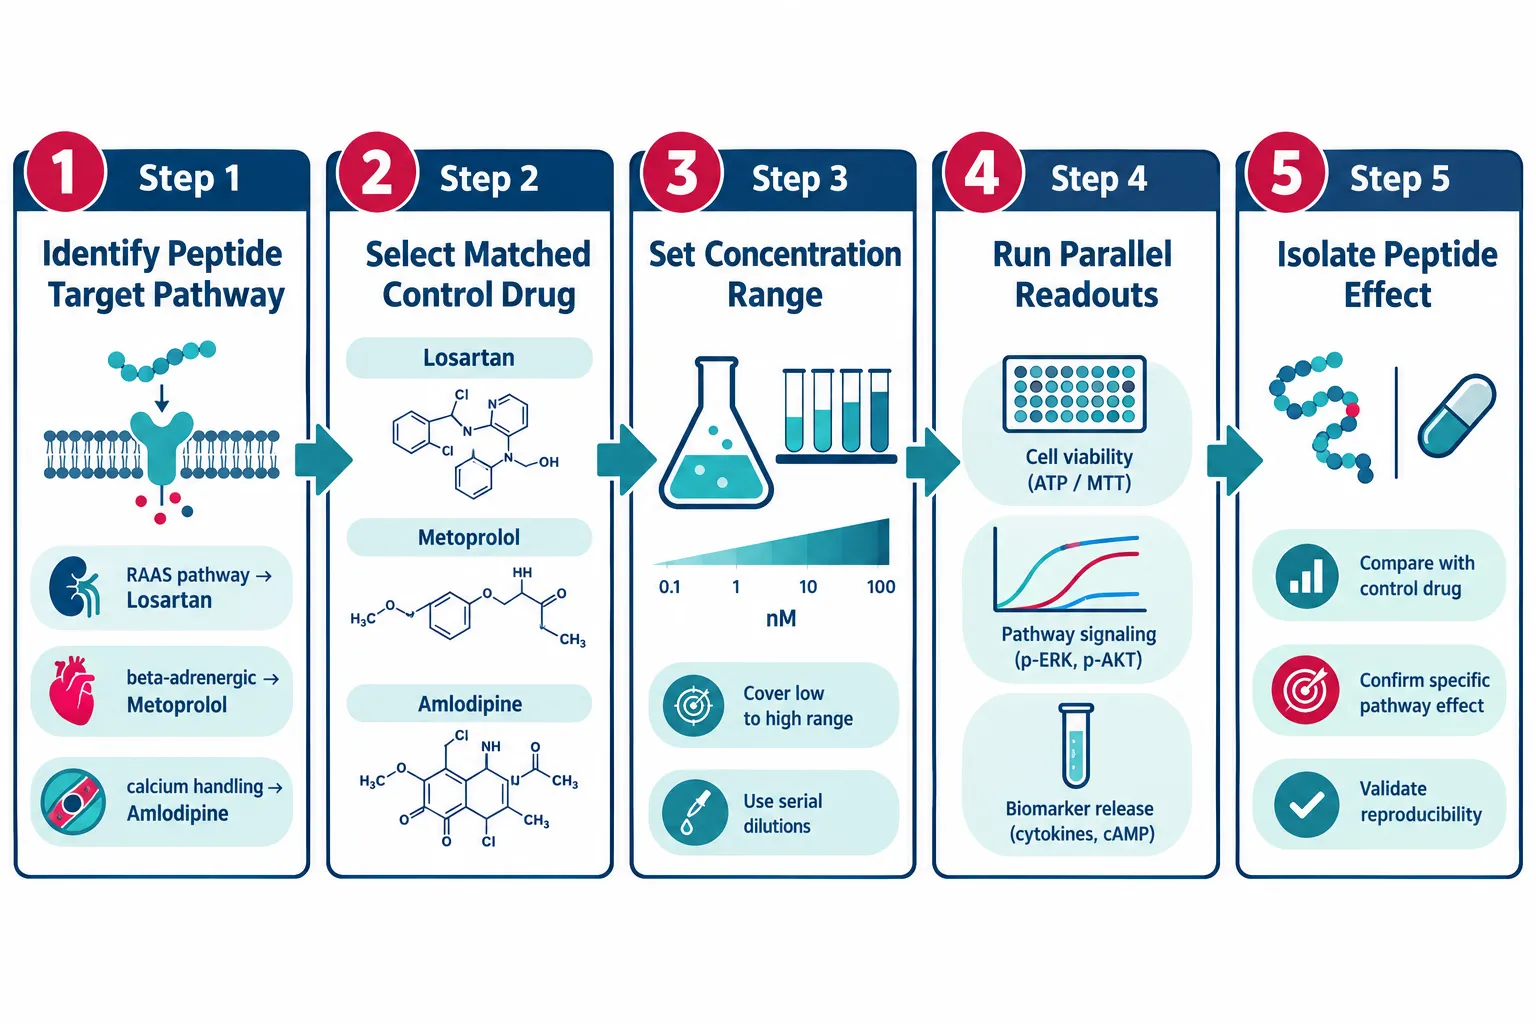
The phrase "positive control" is often used loosely in peptide research. In cardiovascular contexts, a true control arm must share the target pathway of the experimental compound, not merely produce a measurable hemodynamic effect. Amlodipine, metoprolol, and losartan in peptide experiments serve as mechanistic anchors, each isolating a separate axis of cardiovascular regulation.

Amlodipine blocks L-type voltage-gated calcium channels in cardiomyocytes and vascular smooth muscle. It is the appropriate control when a peptide is expected to alter intracellular calcium handling, reduce vascular tone through calcium-dependent mechanisms, or modulate excitation-contraction coupling. Studies examining SS-31 analogs or mitochondria-targeted peptides with cardiac calcium implications, for example, benefit directly from an amlodipine reference arm. For researchers sourcing materials for such models, reviewing SS-31 10mg research peptide considerations provides useful background on experimental framing.

Metoprolol, a selective beta-1 adrenergic receptor antagonist, is the logical control for peptides that intersect sympathetic nervous system signaling, heart rate, cAMP-PKA pathways, or cardiomyocyte survival under adrenergic stress. Growth-hormone secretagogues and ghrelin-axis peptides can activate signaling cascades that overlap with adrenergic pathways, making metoprolol a relevant comparator. Understanding peptide half-life considerations also informs dosing schedules when aligning a peptide's exposure window with metoprolol's pharmacodynamic duration.

Losartan, an angiotensin II type-1 receptor antagonist, belongs in experiments involving natriuretic peptides, wall-stress signaling, or RAAS-interacting compounds. Retatrutide and other multi-receptor peptides show hemodynamic effects that partially overlap with RAAS modulation; losartan quantifies that component. Researchers exploring the GLP-3 peptide signaling pathway will find that angiotensin-receptor control arms help isolate GLP-receptor-specific effects from broader vasoregulatory noise.


Concentration Ranges and Key Readouts
Concentration Ranges and Key Readouts

Selecting the right drug is only half the problem. Using it at a physiologically and experimentally relevant concentration is equally critical.

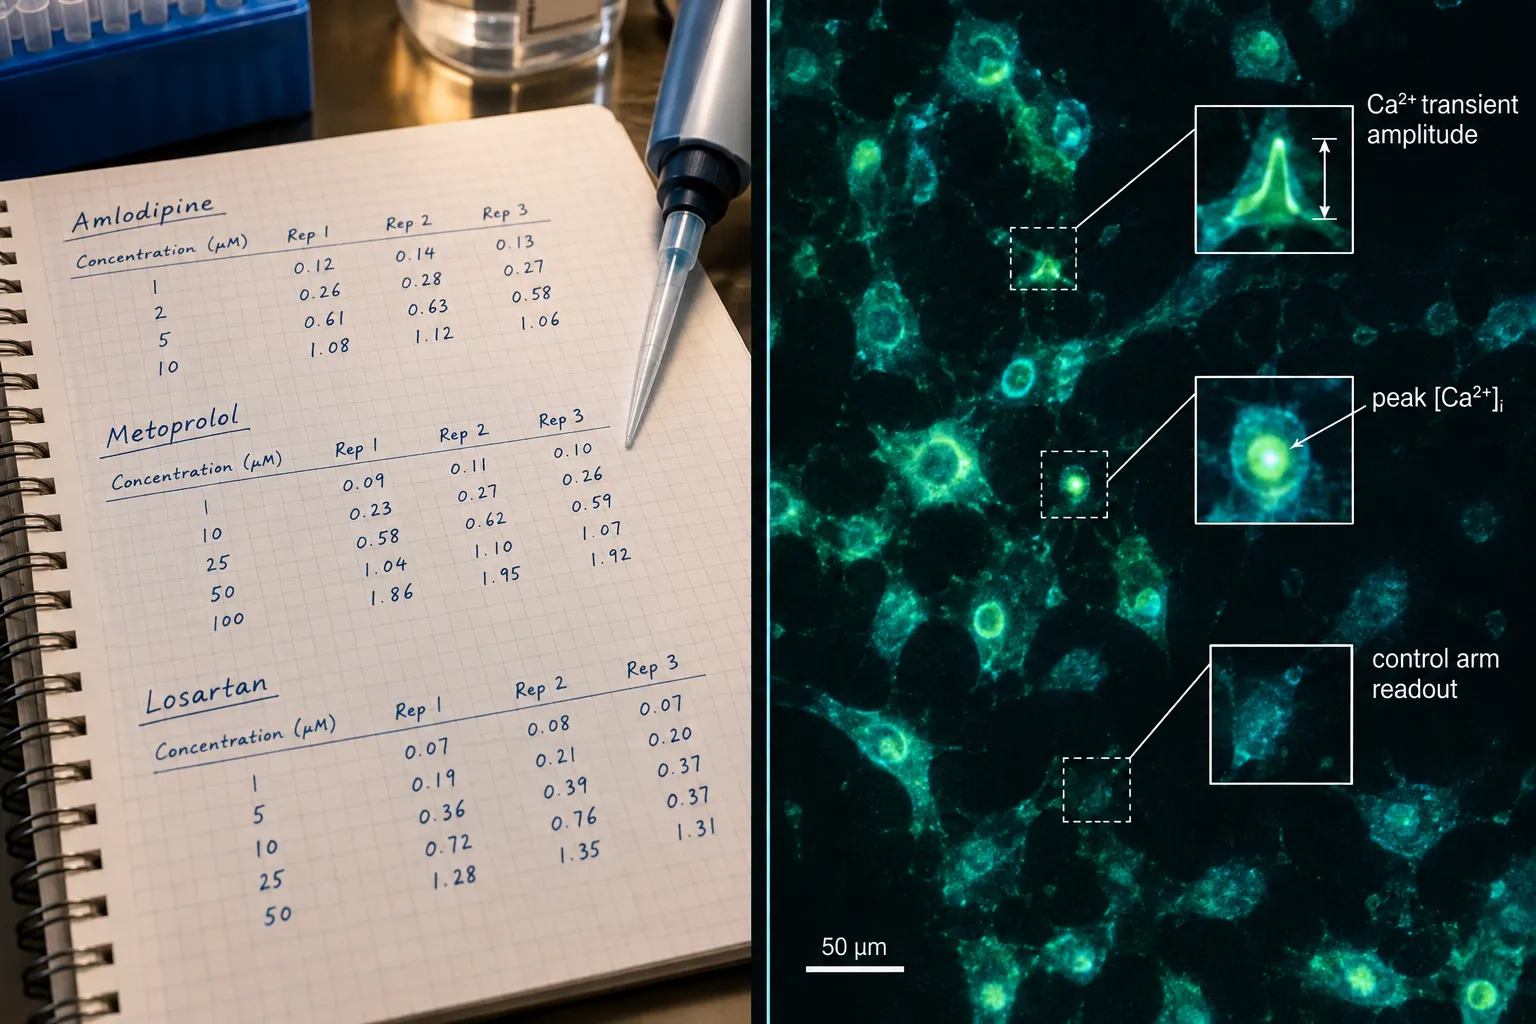
Standard in vitro working ranges:

Drug Typical In Vitro Range Primary Readout
Amlodipine 1-10 µM Peak [Ca2+]i, L-type current amplitude
Metoprolol 1-100 µM cAMP levels, heart rate (in intact preparations)
Losartan 1-50 µM BNP/ANP secretion, MAPK phosphorylation

These ranges should bracket the concentration-response curve of the experimental peptide. If a peptide is tested at 10 nM to 1 µM, the control drug should also span a comparable effect range so that the comparison is meaningful rather than arbitrary.

Readouts deserve equal attention. For calcium-handling studies, peak calcium transient amplitude and sarcoplasmic reticulum load mirror the readouts used with amlodipine directly. For beta-adrenergic work, cAMP quantification and phospholamban phosphorylation status are standard. For RAAS-oriented experiments, brain natriuretic peptide secretion and ERK1/2 activation are well-validated endpoints.

Researchers building rigorous benchmarking workflows should consult resources on Bachem and reference standards for building robust peptide benchmarks to ensure the purity and characterization of both control and experimental compounds meet publication-grade standards.


Practical Framework for Choosing Among the Three Agents
Practical Framework for Choosing Among the Three Agents

The following decision logic applies when designing control arms for cardiovascular peptide experiments:

  1. Map the peptide's suspected receptor target. Does it bind a GPCR linked to Gq/calcium, Gs/cAMP, or a receptor tyrosine kinase with downstream RAAS crosstalk?
  2. Select the drug that blocks the same downstream node. Calcium node → amlodipine. cAMP/adrenergic node → metoprolol. Angiotensin/wall-stress node → losartan.
  3. Consider multi-pathway peptides. Retatrutide acts on GLP-1R, GIP-R, and glucagon receptors simultaneously. Its hemodynamic profile may require both a losartan arm (for RAAS overlap) and a metoprolol arm (for sympathetic activation overlap). Using a single control drug in a multi-receptor study risks misattributing effects.
  4. Avoid confounded control arms. Running amlodipine alongside a peptide that has no known calcium-channel interaction adds noise without interpretive value. Worse, a pharmacodynamically mismatched control can create an apparent "superiority" for the peptide that reflects the control's irrelevance rather than the peptide's potency.

For GLP-axis peptides specifically, cross-referencing the GLP-1 peptide buy: generational research concepts and sourcing notes page helps contextualize which receptor subtypes are relevant when choosing angiotensin versus adrenergic controls.

Similarly, researchers working on BPC-157 or TB-500 vascular regeneration studies should align control arm selection with documented angiogenic and adrenergic crosstalk. The TB-500 buy: controlled experimental models and QC workflow resource addresses model-selection principles that apply directly to control arm design.

Key principle: A control arm that cannot be mechanistically explained in the methods section is not a control arm, it is a variable.


Conclusion

Implementing amlodipine, metoprolol, and losartan in peptide experiments is most effective when each agent is matched precisely to the target pathway under investigation. Amlodipine anchors calcium-handling studies, metoprolol isolates adrenergic and survival signaling comparisons, and losartan controls for RAAS and natriuretic peptide pathway contributions.

Actionable next steps for researchers in 2026:

  • Before finalizing a protocol, map the peptide's receptor-to-effector cascade and identify which of the three drug mechanisms overlaps with it.
  • Use published concentration-response data for each control drug to set bracketing doses that match the peptide's tested range.
  • For multi-receptor peptides like retatrutide, consider running two control arms in parallel rather than choosing a single agent.
  • Document the mechanistic rationale for control arm selection explicitly in the methods section to satisfy peer-review scrutiny.
  • Maintain compound purity documentation for both control drugs and experimental peptides to ensure readout differences reflect biology, not chemistry.

Rigorous control arm selection does not slow experiments, it is what makes their results interpretable.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/amlodipine-metoprolol-and-losartan-in-peptide-experiments-choosing-cardiovascula.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-21 13:05:202026-10-21 13:05:20Amlodipine, Metoprolol, and Losartan in Peptide Experiments: Choosing Cardiovascular Control Arms
Tesamorelin and Ipamorelin Peptides: Separating GH-Pulse, Visceral-Fat, and Body-Composition Readouts

Tesamorelin and Ipamorelin Peptides: Separating GH-Pulse, Visceral-Fat, and Body-Composition Readouts

October 17, 2026/0 Comments/in Uncategorized/by

Visceral fat responds to growth hormone secretagogues in measurably different ways depending on which peptide drives the GH signal, yet most community protocols treat tesa and ipamorelin as interchangeable tools. Tesamorelin and Ipamorelin Peptides: Separating GH-Pulse, Visceral-Fat, and Body-Composition Readouts is not just a labeling exercise; it is a prerequisite for designing experiments or interpreting outcomes with any confidence. Without isolating each variable, researchers risk attributing fat-loss effects to a peptide that has no proven capacity to produce them.

Key Takeaways

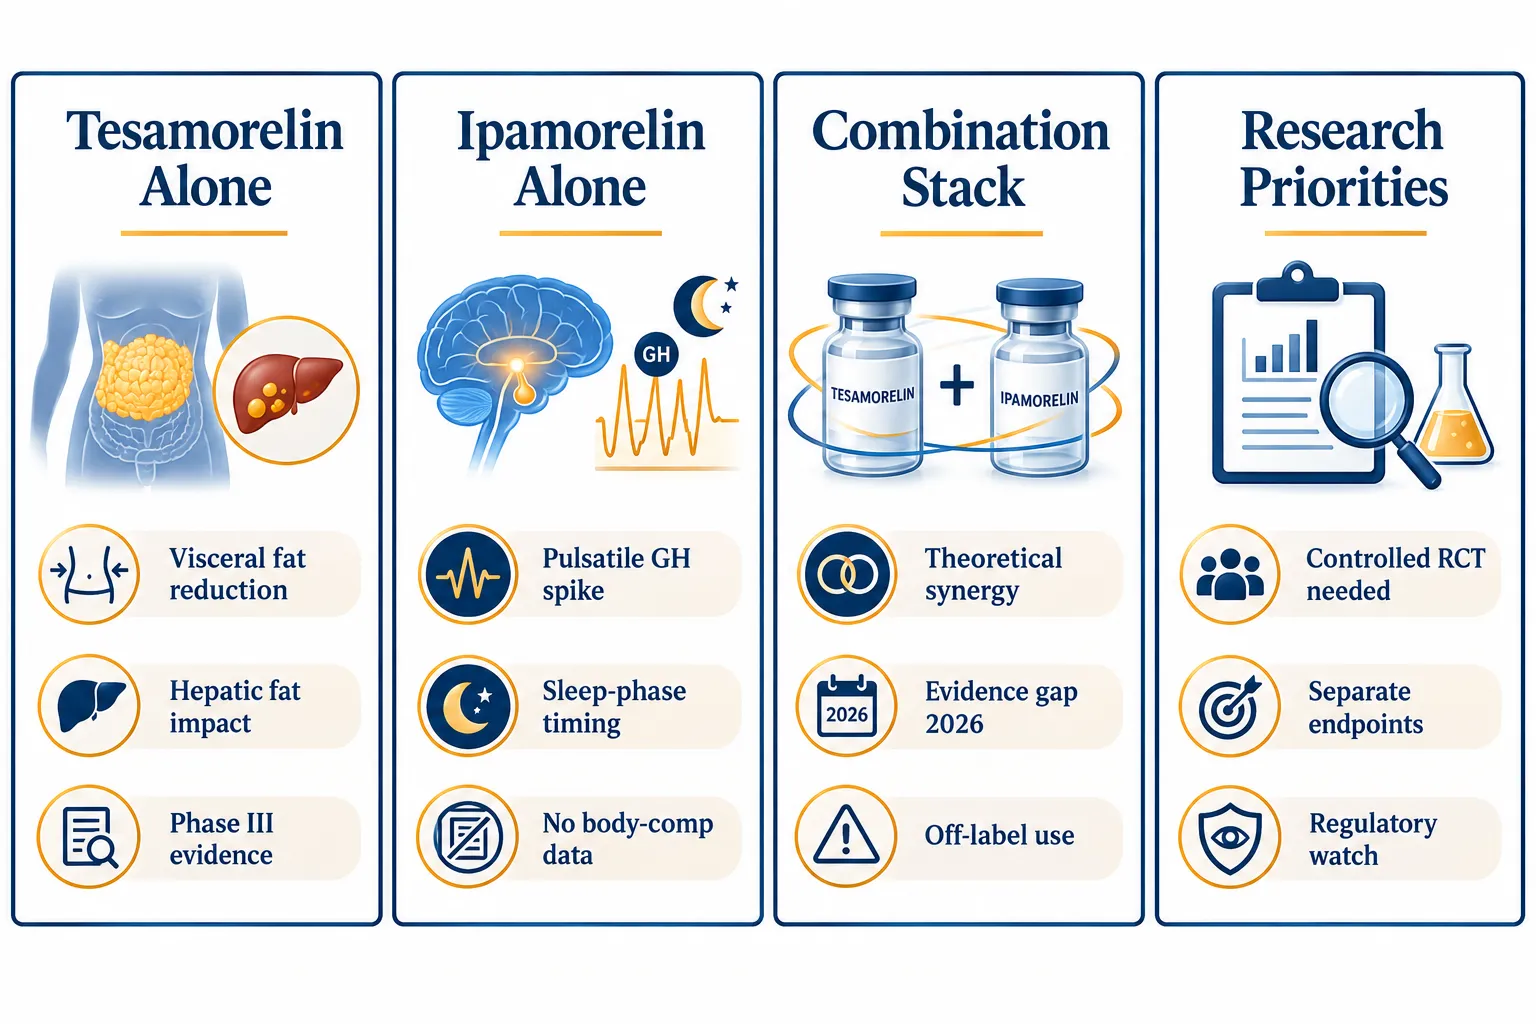
  • Tesamorelin is an FDA-approved GHRH analog with robust Phase III evidence for visceral and hepatic fat reduction; ipamorelin is a ghrelin mimetic with no equivalent body-composition data.
  • Ipamorelin produces sharp, selective GH pulses with minimal cortisol or prolactin spillover, making it useful for studying pulsatility, not fat mobilization.
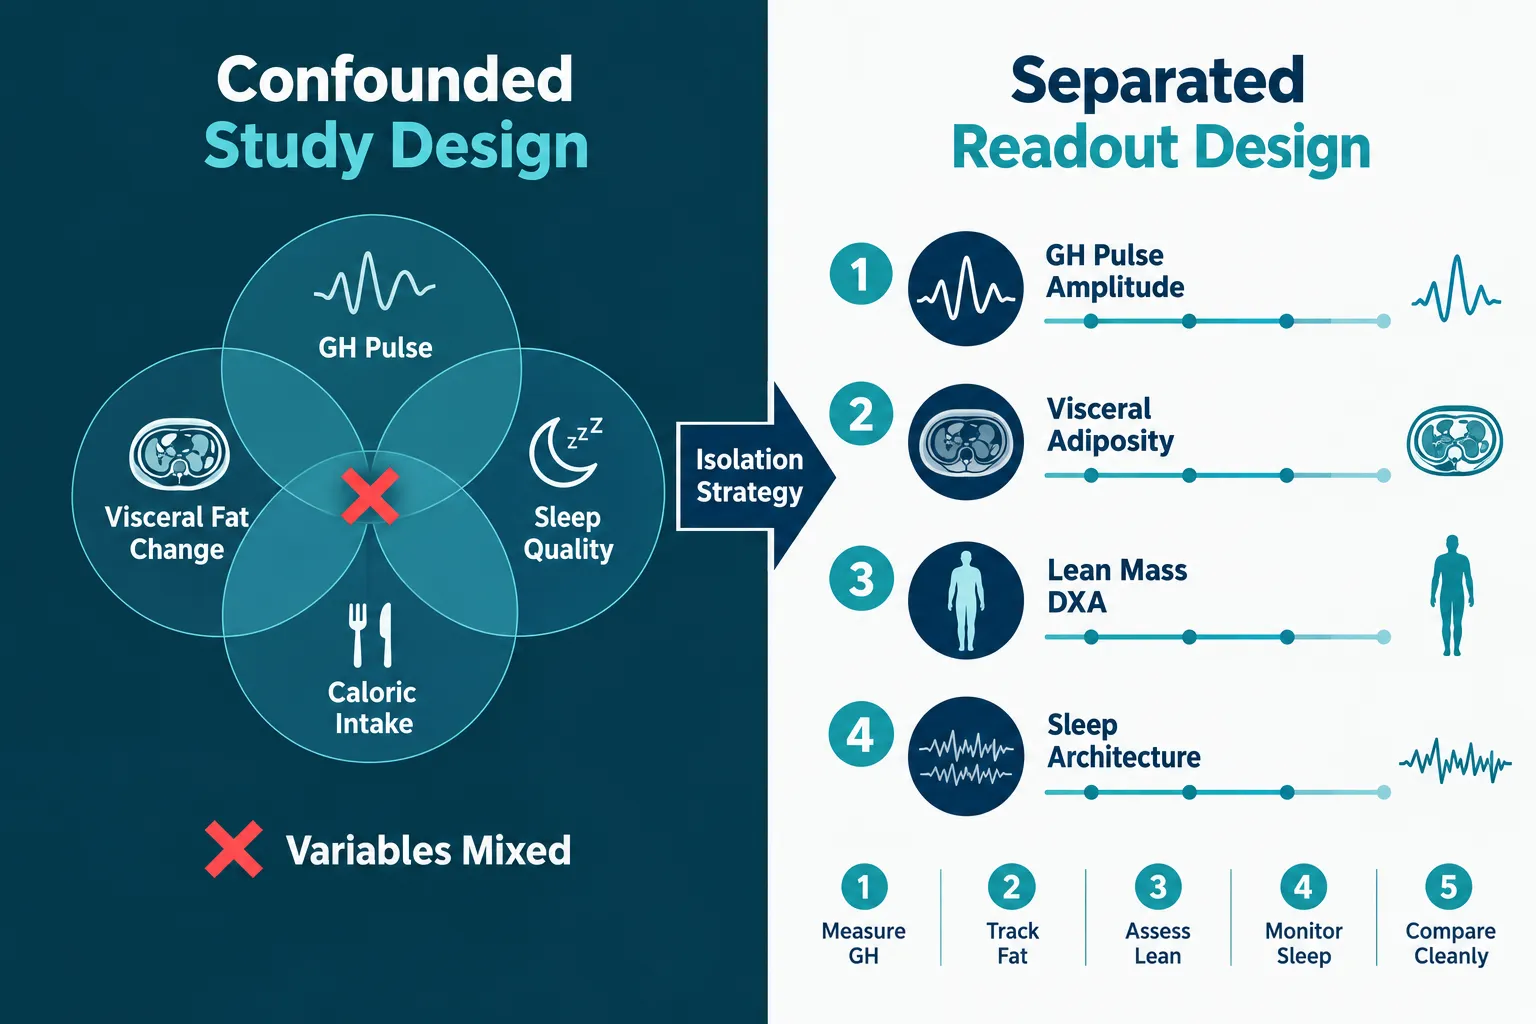
  • Confounding variables, sleep quality, caloric intake, lean mass changes, must be measured independently to isolate each peptide's true contribution.
  • Combination stacks of tesa and ipamorelin are growing in the research market, but controlled evidence for additive or synergistic effects remains absent as of 2026.
  • Experimental design, not anecdote, is the only reliable path to separating GH-pulse readouts from visceral-fat and body-composition outcomes.

Mechanism Differences That Define the Experimental Problem

Mechanism Differences That Define the Experimental Problem

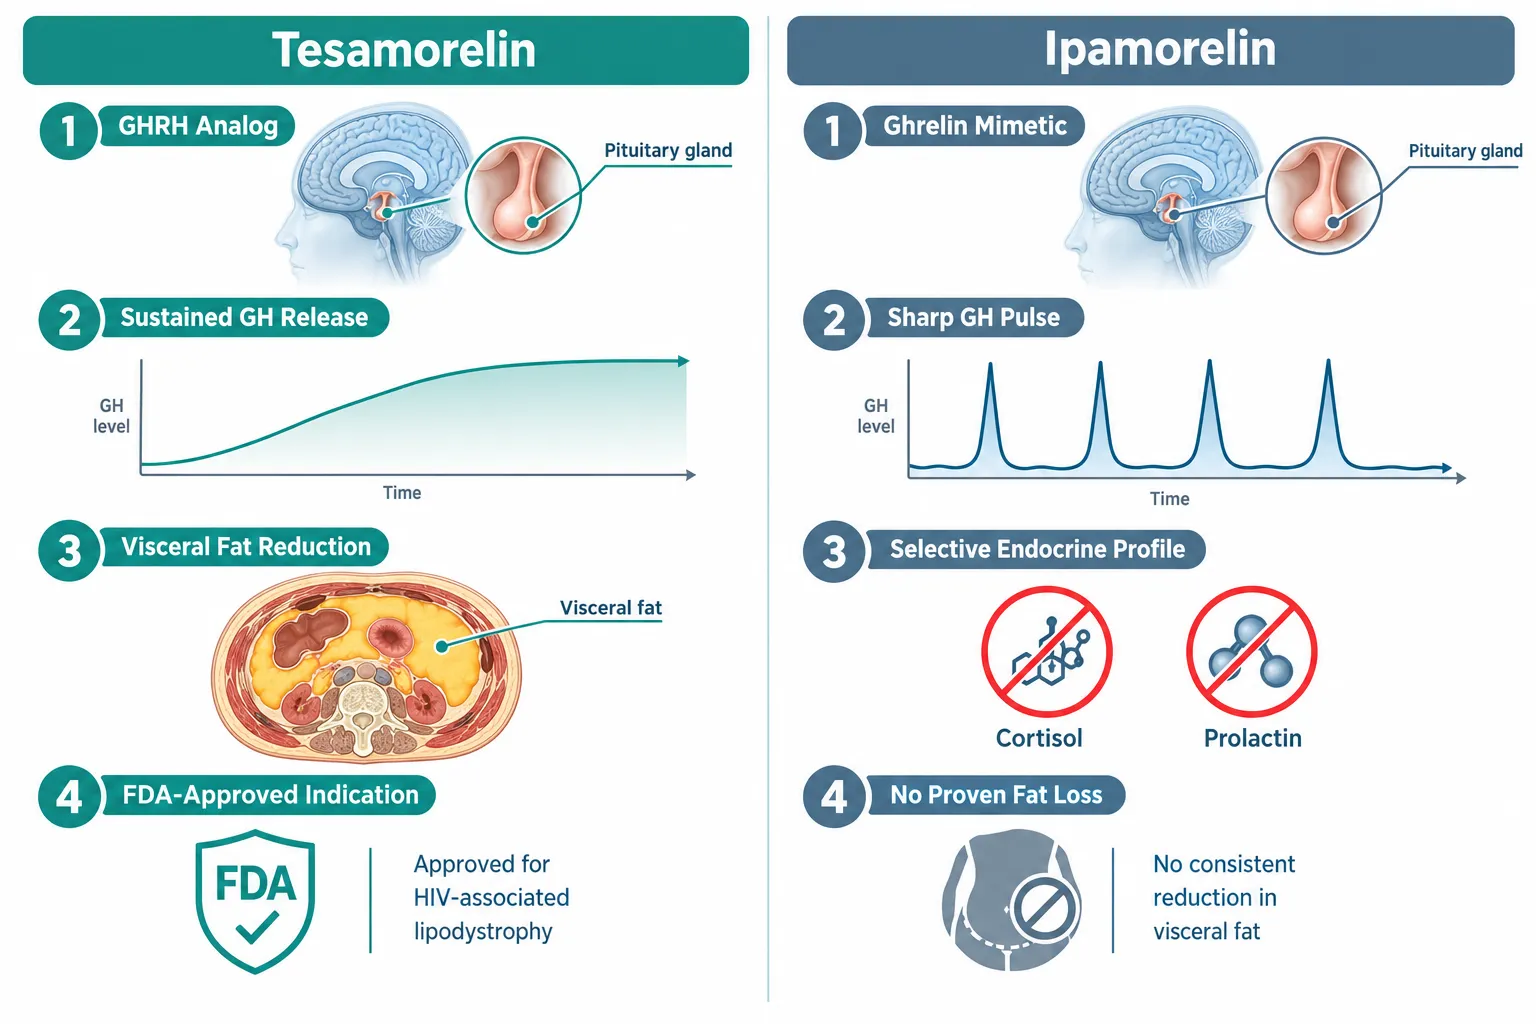
Tesamorelin is a synthetic analog of growth hormone-releasing hormone (GHRH). It binds pituitary GHRH receptors and stimulates a sustained, physiologically shaped GH release. Its approved indication covers HIV-associated lipodystrophy, where Phase III trials documented significant reductions in visceral adipose tissue (VAT) and hepatic fat. Importantly, a post-hoc Phase III analysis confirmed that efficacy held regardless of whether subjects presented with dorsal fat accumulation, meaning the fat-loss signal was not an artifact of a specific phenotype.

Ipamorelin operates through a different receptor class entirely. As a ghrelin mimetic and growth hormone secretagogue receptor (GHSR) agonist, it triggers a sharp, high-amplitude GH pulse. What distinguishes it from older secretagogues such as GHRP-6 is its endocrine selectivity: cortisol and prolactin remain largely unaffected at standard doses. Animal studies and surgical-patient data confirm that ipamorelin's pulsatile output is real and reproducible, but no controlled human trial has linked those pulses to meaningful reductions in VAT, subcutaneous fat, or improvements in lean mass.

This mechanistic divergence is the central experimental problem. When both peptides are administered together, any observed body-composition change cannot be cleanly attributed to either agent without a study design that isolates the variables.

For researchers exploring Tesamorelin as a standalone compound, understanding this distinction is foundational before adding any secondary secretagogue.


Designing Studies That Separate GH-Pulse, Visceral-Fat, and Body-Composition Readouts

Designing Studies That Separate GH-Pulse, Visceral-Fat, and Body-Composition Readouts

The phrase "Tesamorelin and Ipamorelin Peptides: Separating GH-Pulse, Visceral-Fat, and Body-Composition Readouts" describes an active methodological challenge. Four variables routinely confound each other in poorly designed protocols:

1. GH pulse amplitude and timing
Ipamorelin's GH spike peaks within 15-30 minutes of administration and clears rapidly. Tesamorelin produces a broader, more sustained curve. Measuring both with serial serum GH sampling requires time-stamped blood draws that align with each peptide's pharmacokinetic window, not a single morning trough.

2. Visceral and hepatic adiposity
Tesamorelin's documented effect is specifically on VAT and liver fat, not subcutaneous fat. MRI or CT cross-sectional imaging at L4-L5 is the accepted readout. DXA alone will miss the visceral compartment. Studies that report only total body fat percentage cannot confirm a tesa-specific effect.

3. Lean mass changes
GH promotes protein synthesis. Any gain in lean mass will alter the body-composition ratio independent of fat loss. DXA with regional analysis separates appendicular lean mass from trunk fat, providing a cleaner readout.

4. Sleep quality and caloric intake
GH secretion is tightly coupled to slow-wave sleep. Ipamorelin is frequently dosed at bedtime precisely to align with natural nocturnal GH release. If sleep quality improves, or if subjects reduce caloric intake during a study period, both variables independently affect body composition. Neither is controlled for in most community-reported protocols.

A properly designed experiment would include:

  • Baseline and endpoint MRI for VAT
  • Serial GH sampling matched to each peptide's peak window
  • DXA with regional lean-mass analysis
  • Validated sleep-quality instruments (e.g., polysomnography or actigraphy)
  • Standardized dietary intake logging

Researchers reviewing CJC-1295 Ipamorelin cycle protocols will recognize that most community designs omit at least three of these five elements.


The Combination Stack: Evidence Gap and Practical Considerations

The Combination Stack: Evidence Gap and Practical Considerations

By October 2026, blended formulations pairing tesa with ipamorelin, sometimes alongside CJC-1295 or AOD-9604, have become a notable segment of the research-peptide market. The theoretical rationale is straightforward: tesa provides the GHRH signal, ipamorelin provides a complementary GHSR pulse, and together they may produce a more complete GH secretory pattern than either alone.

The evidence gap, however, is substantial. No published randomized controlled trial has tested this combination in humans for visceral fat, lean mass, or metabolic endpoints. The synergy argument is mechanistically plausible but remains unverified.

Endpoint Tesamorelin Evidence Ipamorelin Evidence Combination Evidence
Visceral fat reduction Phase III RCT confirmed None None
Hepatic fat reduction RCT data available None None
GH pulse amplitude Moderate, sustained High, sharp Theoretical additive
Lean mass change Modest, documented Animal data only None
Safety in combination Unknown Unknown Unknown

For researchers comparing secretagogue options, the Tesamorelin vs Sermorelin comparison offers useful context on how GHRH analogs differ in potency and indication before layering in a second agent.

Those working with multi-peptide blends can review formulation details such as the Tesamorelin AOD9604 CJC1295 Ipamorelin 12mg blend to understand what components are present, while recognizing that the body-composition evidence base applies only to tesa as a single agent.

Regulatory commentary in 2026 continues to flag GH-axis manipulation through off-label stacks as an area requiring closer scrutiny, particularly regarding long-term IGF-1 elevation and insulin sensitivity.

For those assessing the broader peptide landscape, resources on what is the strongest peptide for weight loss provide comparative context across multiple compound classes.


Conclusion

Separating GH-pulse readouts from visceral-fat and body-composition outcomes is not a semantic distinction, it determines whether experimental data is actionable or misleading. Tesamorelin carries the only robust human evidence for targeted VAT reduction among GH secretagogues. Ipamorelin contributes a selective, reproducible GH pulse with a clean endocrine profile, but that pulse has not been linked to meaningful fat loss in controlled settings.

Actionable next steps for researchers:

  • Design protocols with endpoint-specific measurement tools: MRI for VAT, DXA for lean mass, serial GH sampling for pulse characterization.
  • Control for sleep quality and caloric intake as independent variables before attributing body-composition changes to any peptide.
  • Treat combination stacks as hypothesis-generating, not evidence-based, until RCT data exists.
  • Consult CJC-1295 Ipamorelin assay planning resources when structuring multi-peptide assays to ensure sourcing and measurement integrity.
  • Review Tesamorelin vs Sermorelin comparisons to benchmark tesa's evidence profile against other GHRH analogs before selecting a research compound.

The field will advance only when experimental design matches the complexity of the biology, and that starts with measuring the right outcome for the right peptide.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/tesa-and-ipamorelin-peptides-separating-gh-pulse-visceral-fat-and-body-co.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-17 13:04:592026-10-17 13:04:59Tesamorelin and Ipamorelin Peptides: Separating GH-Pulse, Visceral-Fat, and Body-Composition Readouts
CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts

CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts

October 5, 2026/0 Comments/in Uncategorized/by

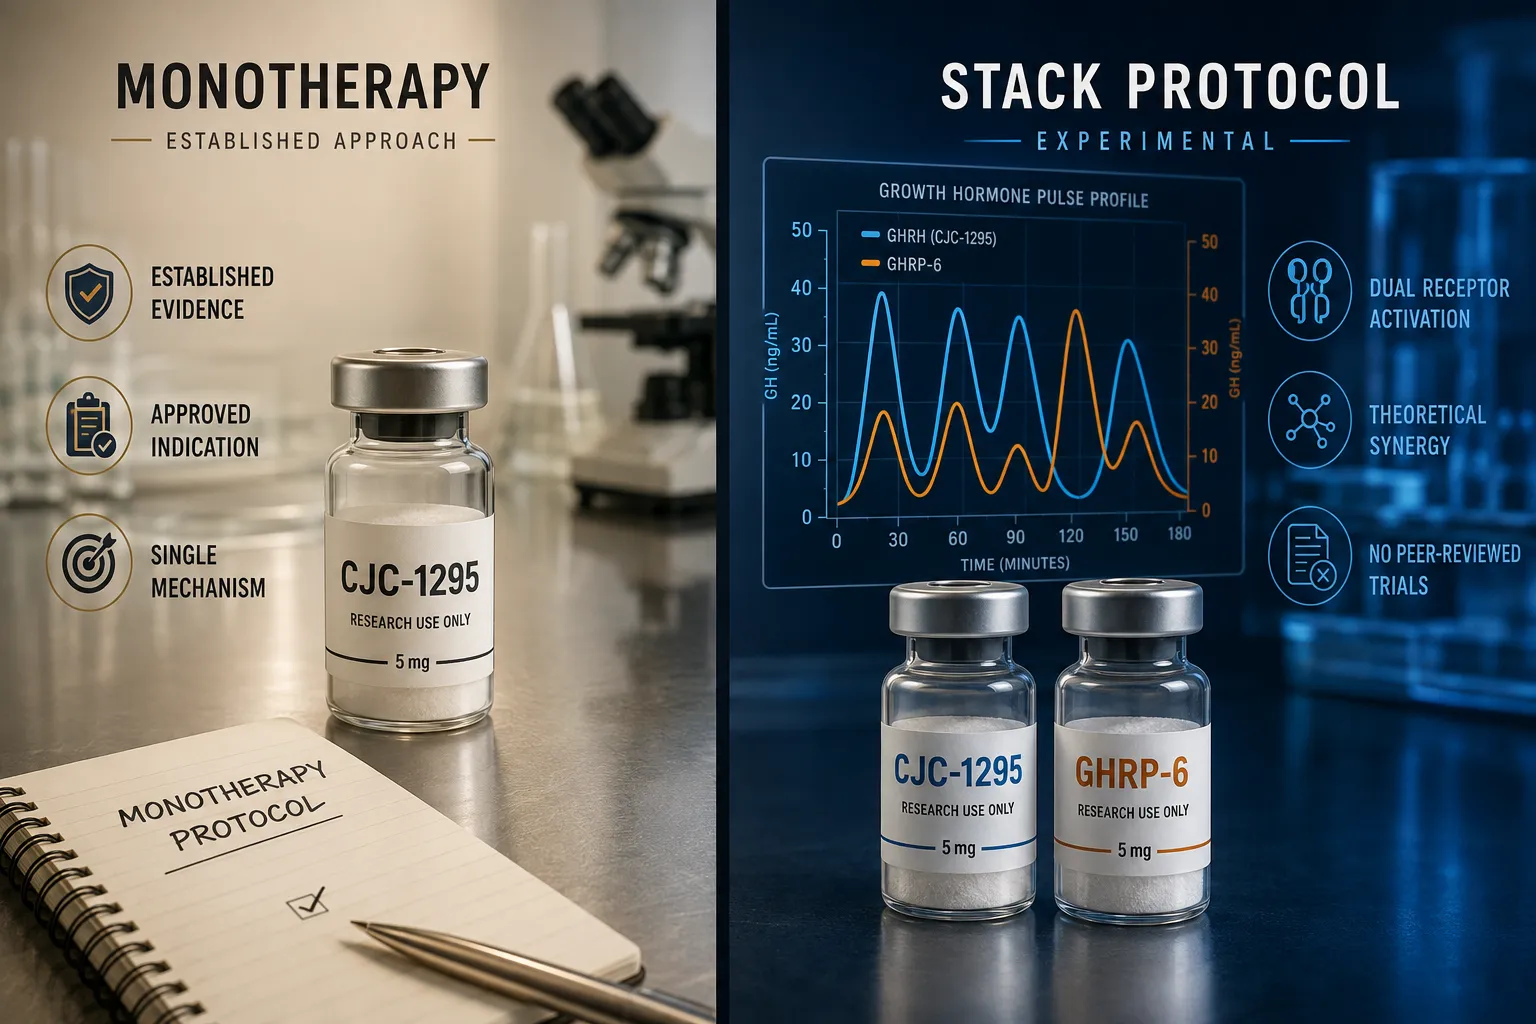
Clinic-based reports consistently describe 3- to 5-fold increases in GH pulse amplitude when CJC-1295 is paired with ipamorelin, yet as of 2026, not a single published randomized controlled trial has tested the combination in humans. That gap between widespread clinical use and rigorous experimental evidence is not a minor footnote. It means that nearly every claim about "synergistic" or "additive" GH pulses from this blend is built on data that cannot cleanly distinguish true pharmacodynamic interaction from artifacts of dosing schedule, peptide form, meal timing, and background GH status.

Understanding CJC-1295 with ipamorelin: how to separate additive GH-pulse effects from blend and timing artifacts requires a disciplined study-design framework, one that treats synergy as a hypothesis to test, not a starting assumption.

Key Takeaways

  • No RCT has directly tested the CJC-1295 plus ipamorelin combination; all GH-pulse data are clinic-based or extrapolated from single-agent studies.
  • Using CJC-1295 with DAC creates a sustained GH elevation lasting days, which can masquerade as pulse synergy and must be avoided in pulse-focused research.
  • A 2×2 factorial design with vehicle controls is the minimum study architecture needed to isolate true additive GH-pulse effects from timing and exposure artifacts.
  • Fasted pre-sleep dosing and consistent circadian phase-locking reduce meal- and sleep-related variability that inflates apparent pulse amplitude.
  • Staggered dosing intervals (CJC-1295 first, ipamorelin 15-30 minutes later) versus simultaneous injection offer a practical within-subject comparison of pulse shape and kinetics.

Why the Peptide Form Changes Everything

Why the Peptide Form Changes Everything

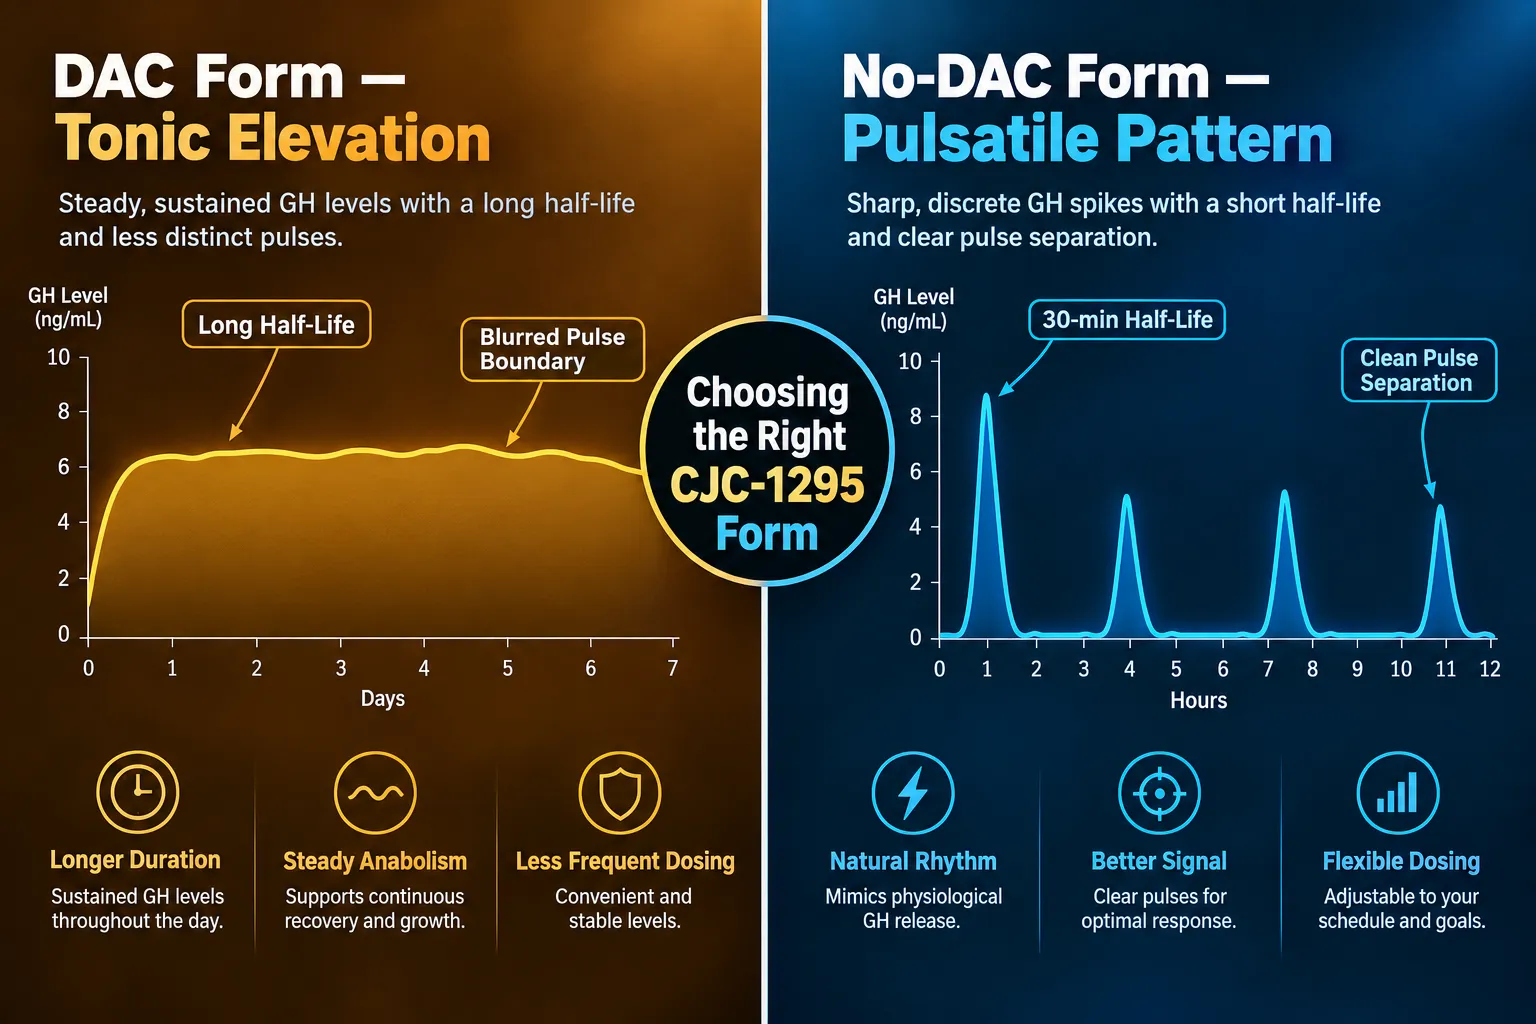
The first design decision, and the most consequential, is which form of CJC-1295 is used. The DAC (Drug Affinity Complex) version binds albumin after injection, extending its half-life to several days. Single subcutaneous doses have produced 2- to 10-fold increases in mean plasma GH lasting six or more days, with IGF-1 elevations persisting 9-11 days. That pharmacokinetic profile is incompatible with pulsatile GH research. When baseline GH is elevated for nearly two weeks, any ipamorelin-triggered spike departs from an already-raised platform, making the combined peak appear larger than it actually is relative to a true resting state.

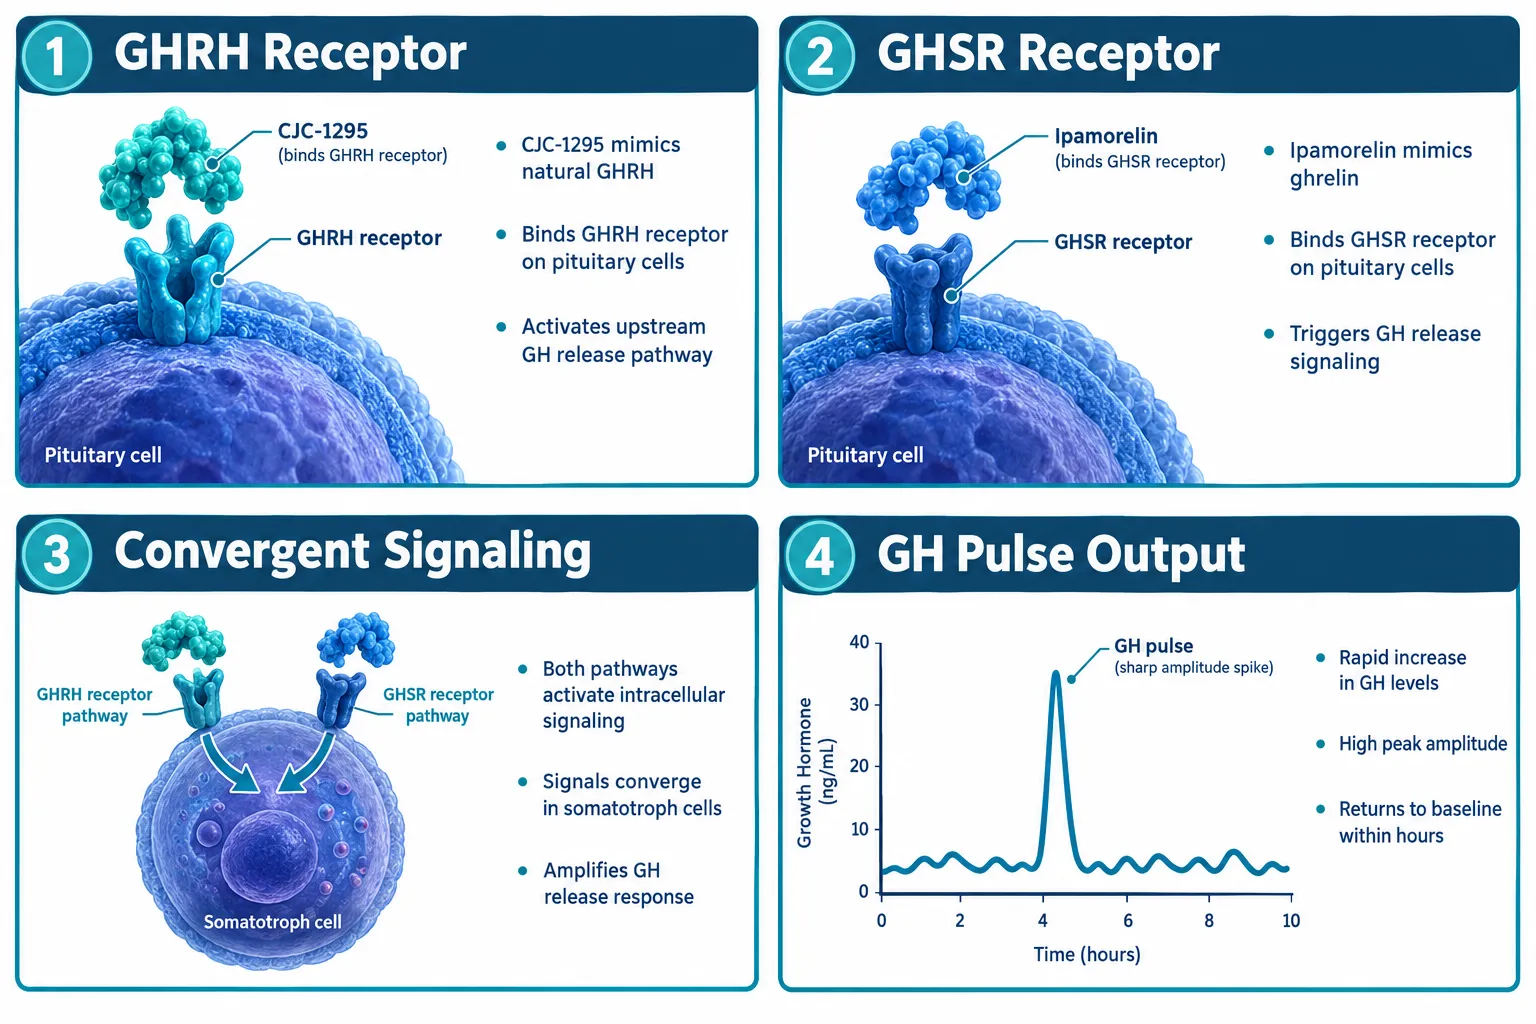
CJC-1295 no-DAC (mod-GRF 1-29) solves this problem. Its reported half-life is roughly 30 minutes. Ipamorelin's half-life is approximately 2 hours. Co-administering the two creates a short, overlapping signaling window that preserves a discrete pulsatile pattern. The GHRH receptor (targeted by CJC-1295) and the growth hormone secretagogue receptor (targeted by ipamorelin) are distinct but convergent pathways at the somatotroph cell. Activating both simultaneously amplifies GH release beyond what either agent achieves alone, but only the no-DAC form keeps that interaction measurable as a clean pulse rather than a tonic elevation.

Anyone exploring the Tesamorelin CJC-1295 Ipamorelin 12mg blend should understand this distinction before interpreting any GH data from a multi-peptide formulation.


A Factorial Study Design for CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts

A Factorial Study Design for CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifa

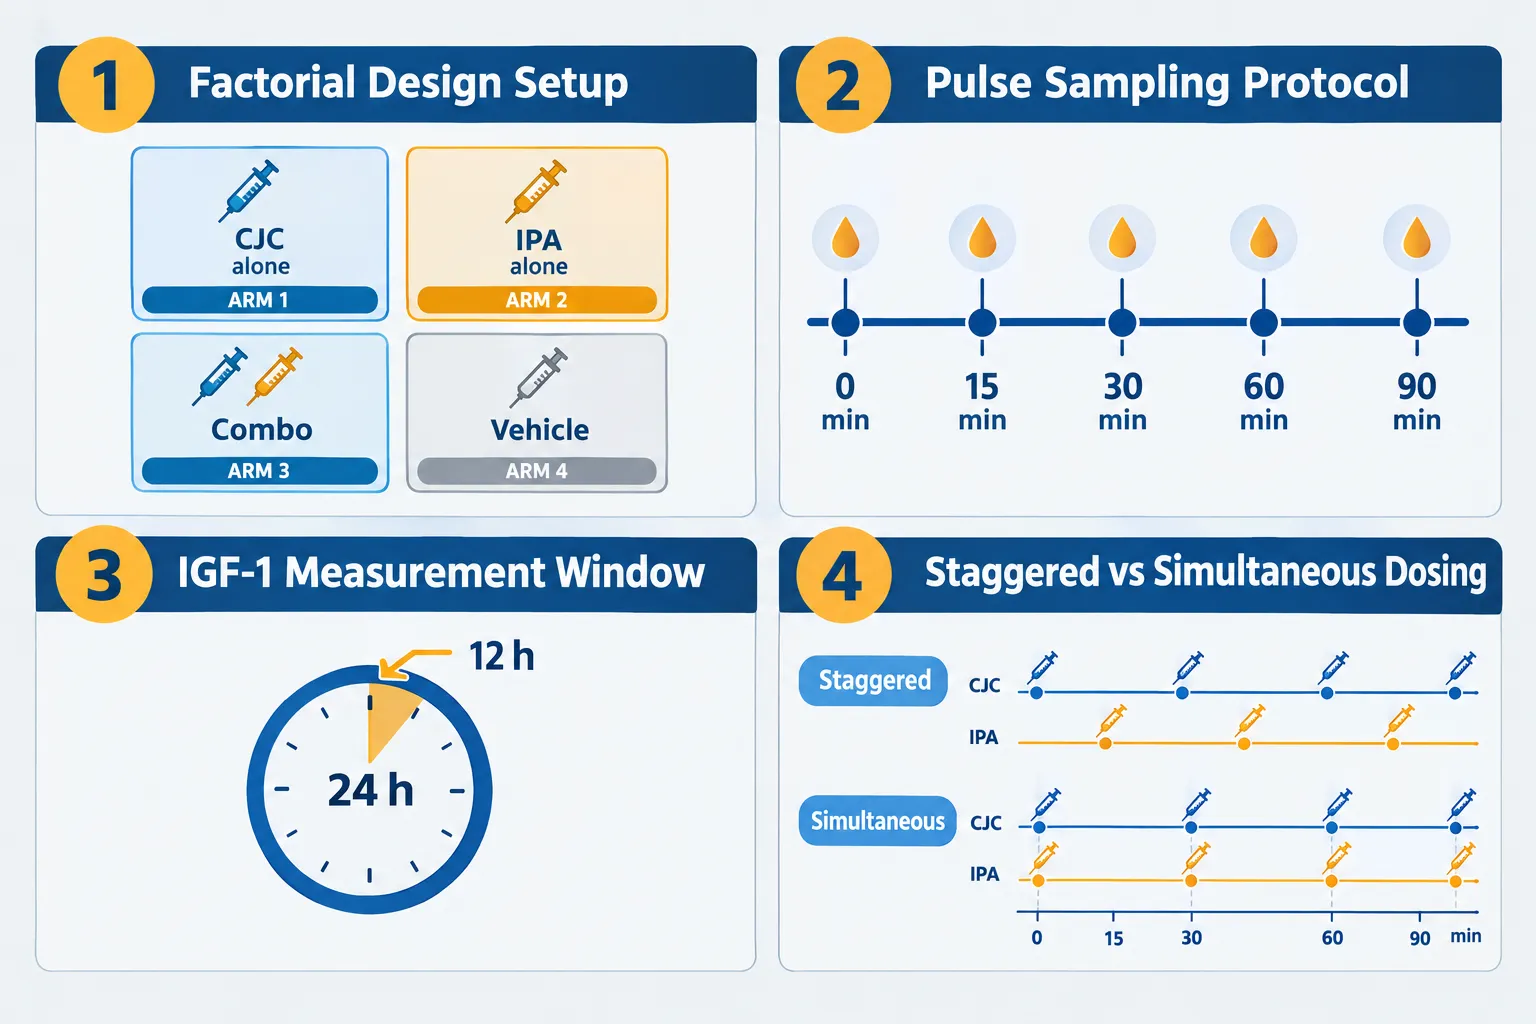
The minimum credible architecture for testing this combination is a 2×2 factorial design with four arms:

Arm CJC-1295 no-DAC Ipamorelin
1 Active Placebo
2 Placebo Active
3 Active Active
4 Placebo Placebo

This structure separates three distinct effects: the CJC-1295 main effect, the ipamorelin main effect, and the interaction term. If the combination arm (Arm 3) produces a GH pulse significantly larger than the sum of Arms 1 and 2 above the vehicle baseline (Arm 4), that constitutes evidence of true synergy. If it simply equals the sum, the effect is additive. If it falls short, there is antagonism or receptor saturation.

Pulse Sampling Protocol

Frequent blood sampling is non-negotiable. A practical schedule draws samples at 0, 15, 30, 45, 60, 90, and 120 minutes post-injection. This captures peak GH amplitude, time-to-peak, and pulse duration, three variables that can each shift independently depending on which agent is used.
IGF-1 timing adds a second layer. Because IGF-1 responds to cumulative GH exposure over 12-24 hours rather than to individual pulses, it should be measured at a fixed interval (typically 12 hours post-injection) across all arms. Comparing IGF-1 across arms that differ only in injection timing, without standardizing this window, is one of the most common sources of artifact in clinic-based data.

Vehicle Controls and Blinding

Vehicle controls (the diluent used for reconstitution, without active peptide) must match the injection volume and subcutaneous route of the active arms. For those reviewing reconstitution protocols for blend formulations, the vehicle composition matters: bacteriostatic water alone versus a buffered saline vehicle can affect subcutaneous absorption rate and therefore pulse timing.


Timing Artifacts and How to Control Them

Timing Artifacts and How to Control Them

Timing is the single largest source of non-pharmacodynamic artifact in GH-pulse studies with this combination. Three variables dominate:

1. Meal timing and insulin. Elevated insulin suppresses GH secretion. Guides updated through late 2026 consistently recommend injecting at least 2 hours after the last meal, particularly after carbohydrate intake. Pre-sleep fasted dosing is the standard recommendation because it aligns with the endogenous nocturnal GH surge and removes meal variability from the equation.

2. Circadian phase-locking. Dosing CJC-1295 no-DAC with ipamorelin in the early evening (roughly 18:00-20:00) can generate a GH spike near 01:00 that mirrors the body's natural GHRH-driven nocturnal surge. When all subjects receive the blend at the same circadian phase, observed differences in pulse amplitude between arms are more likely attributable to receptor co-activation than to random variation in sleep onset or meal timing.

3. Staggered versus simultaneous injection. Because GHRH receptor signaling and GHSR signaling have different kinetic profiles, injecting CJC-1295 no-DAC first and ipamorelin 15-30 minutes later can alter peak height and pulse width compared to a simultaneous injection. Analyzing these patterns within the same subject, a crossover element embedded in the factorial design, is one of the few practical methods currently available to distinguish true additive GH-pulse effects from artifacts of an arbitrary "both-at-once" schedule.

"Synergy claims for this blend rely on modeled receptor interactions and clinic experience rather than direct pulse-profiling RCTs, a distinction that matters enormously for interpreting amplitude data."

Practical dosing ranges reported in protocol literature run from 100 to 300 mcg of each peptide per injection, with titration every 1-2 weeks starting near 100 mcg. Cycles of 8-12 weeks followed by approximately 4 weeks off help preserve receptor sensitivity, a relevant consideration because receptor desensitization between cycles can alter baseline GH and create pseudo-synergy in later measurements. Researchers interested in ipamorelin sourcing can review available ipamorelin products and IPA 10mg formulations for reference-grade material.

For broader context on how ipamorelin compares to other growth hormone secretagogues, the Tesamorelin vs Ipamorelin comparison and Tesamorelin benefits overview provide useful mechanistic background. Those evaluating multi-peptide stacks can also reference Tesamorelin CJC-1295 blend dosage guidance for formulation-specific considerations.

Regulatory Context in 2026

Neither CJC-1295 nor ipamorelin is FDA-approved. Both peptides have been nominated and subsequently withdrawn from the 503A compounding list, meaning the combination is not permitted as a standard compounded product in the U.S. as of 2026. An FDA advisory committee specifically voted against allowing either peptide in routine compounding. This regulatory status reinforces that any GH-pulse data with the blend come from research or off-label clinic use, not from approved therapeutic programs, which further underscores the need for rigorous experimental controls when interpreting those data.


Conclusion

The central challenge with CJC-1295 with ipamorelin, how to separate additive GH-pulse effects from blend and timing artifacts, is fundamentally a study-design problem, not just a dosing question. The actionable steps are clear:

  • Use CJC-1295 no-DAC, not the DAC form, to preserve discrete pulsatile kinetics and prevent sustained baseline elevation from inflating apparent synergy.
  • Implement a 2×2 factorial design with vehicle controls so that main effects and the interaction term can be estimated independently.
  • Standardize timing by phase-locking injections to a consistent circadian window and enforcing a minimum 2-hour post-meal fast before every injection.
  • Sample frequently (at least seven time points over 120 minutes) and measure IGF-1 at a fixed 12-hour interval across all arms.
  • Test staggered versus simultaneous dosing within subjects to characterize how GHRH and GHSR kinetics interact across different injection intervals.

Until a registered trial applies this framework, the 3- to 5-fold pulse amplitude figures circulating in clinic literature should be treated as directional signals rather than confirmed pharmacodynamic facts. The combination may well be synergistic, but proving it requires separating the biology from the schedule.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/cjc-1295-with-ipamorelin-how-to-separate-additive-gh-pulse-effects-from-blend-an.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-05 13:04:402026-10-05 13:04:40CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts
ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues

ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues

September 27, 2026/0 Comments/in Uncategorized/by

Nearly one billion adults worldwide live with hypertension, yet a growing number of researchers are simultaneously exploring growth-hormone secretagogue peptides whose hemodynamic effects remain poorly characterized. That overlap creates a real experimental design problem. When studying ACE inhibitors and research peptides, specifically designing blood-pressure controls around lisinopril and growth-hormone secretagogues, researchers must understand how ACE-pathway modulation shapes blood pressure, renal readouts, and fluid balance, and how those changes can confound or clarify CJC-1295, ipamorelin, and tesa experiments.

Key Takeaways

  • Lisinopril is a long-acting, evidence-backed ACE inhibitor with well-defined effects on blood pressure, cardiac events, and kidney function.
  • Growth-hormone secretagogues such as ipamorelin, CJC-1295, and tesa can cause fluid retention and potential blood-pressure elevation, particularly in stage 2 hypertension.
  • No rigorous human study has directly measured blood-pressure changes attributable to ipamorelin alone, creating a significant data gap.
  • ACE-pathway suppression alters aldosterone levels and glomerular filtration, which directly affects how renal endpoints are interpreted in peptide research.
  • Designing valid research protocols requires establishing stable lisinopril dosing before introducing GH-axis peptides, then monitoring BP at every injection-period review.

How the ACE Pathway Controls Blood Pressure and Renal Readouts

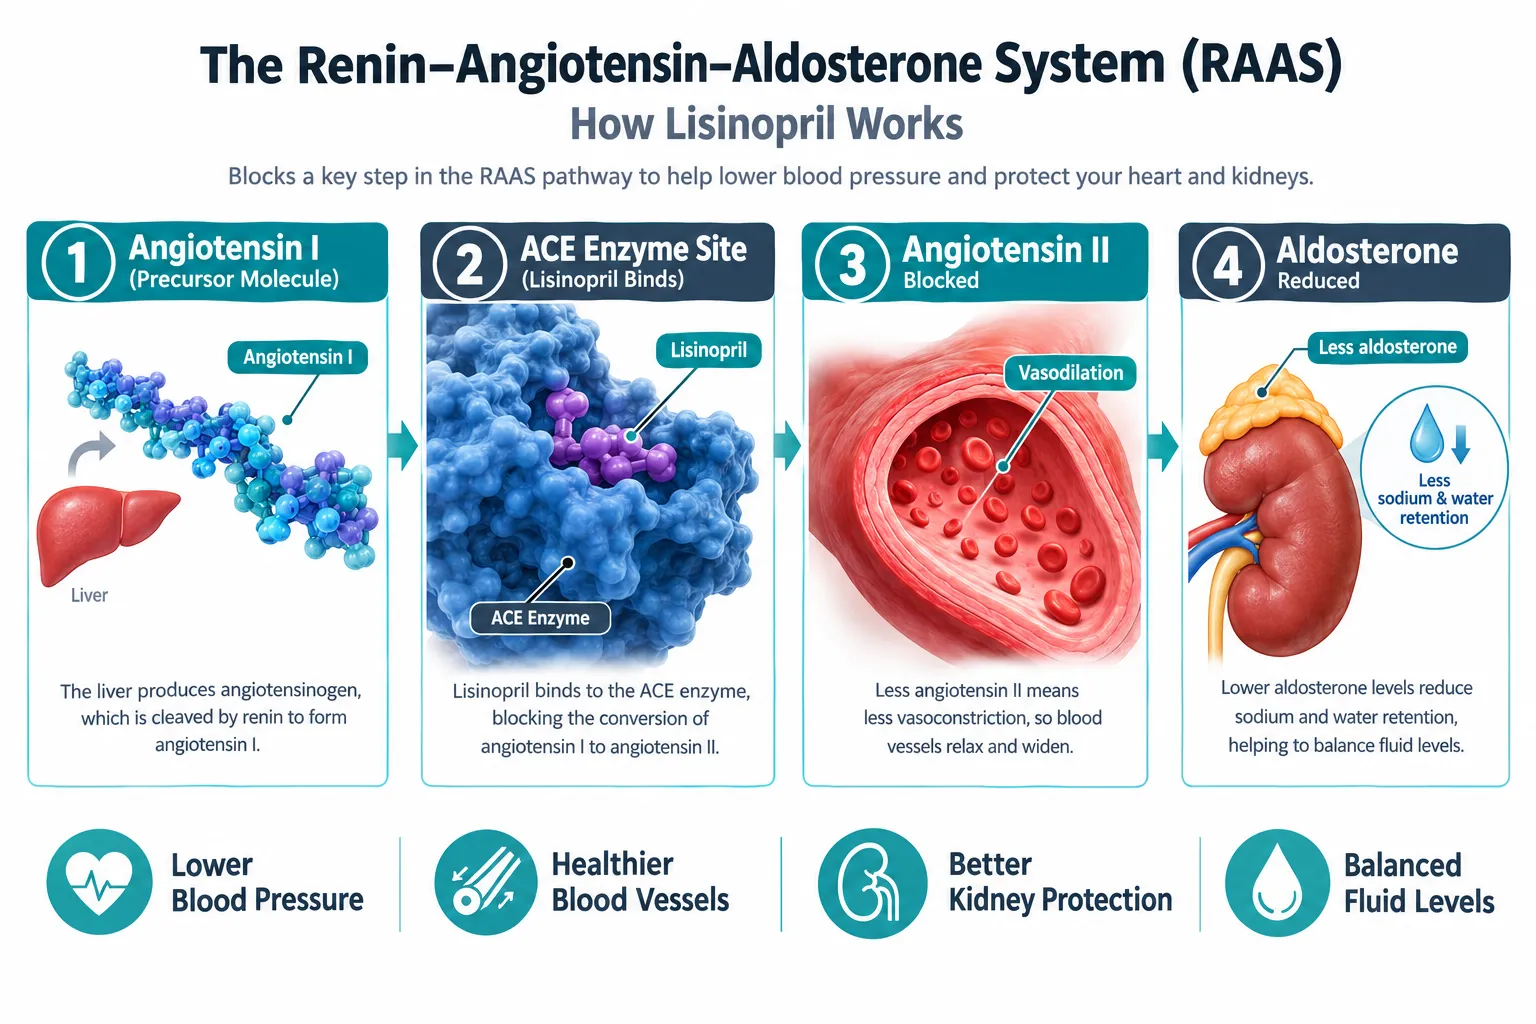
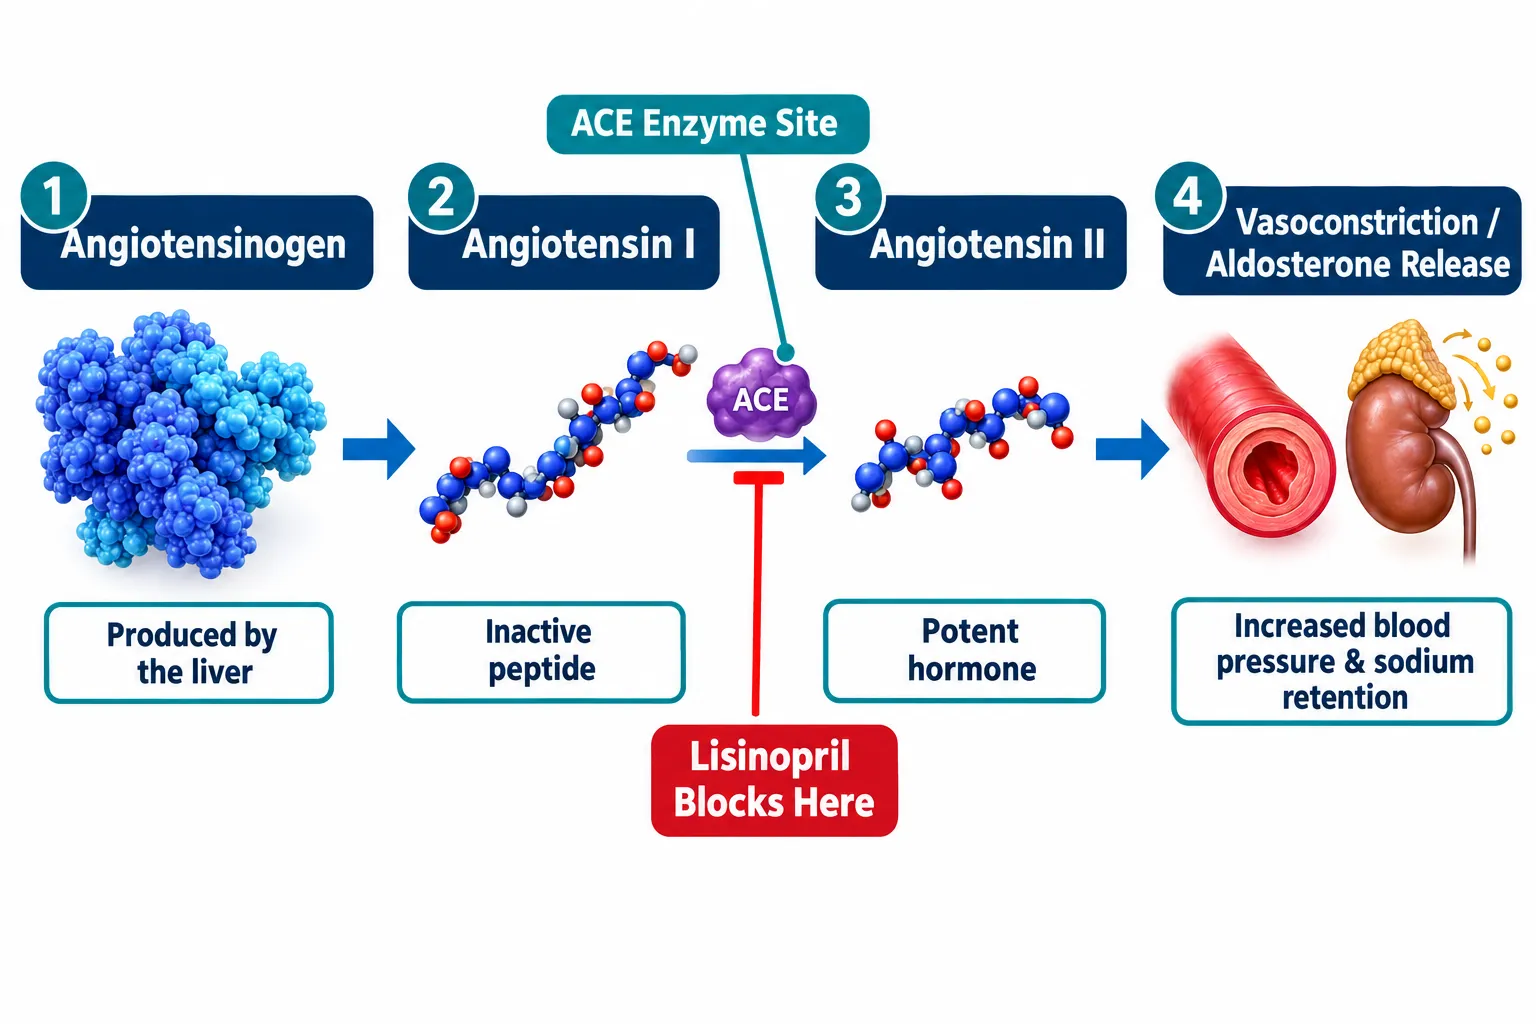
The renin-angiotensin-aldosterone system (RAAS) is the body's primary long-term blood-pressure regulator. Angiotensin-converting enzyme (ACE) converts angiotensin I into angiotensin II, a potent vasoconstrictor that also stimulates aldosterone release. Aldosterone drives sodium and water retention, raising blood volume and pressure.

How the ACE Pathway Controls Blood Pressure and Renal Readouts

Lisinopril blocks this conversion step directly. As an oral, long-acting ACE inhibitor, it is indicated for hypertension, heart failure, post-myocardial infarction management, and proteinuric diabetic kidney disease. Its pharmacological footprint extends well beyond simple vasodilation:

Effect Mechanism Research Relevance
Blood-pressure reduction Reduced angiotensin II, lower vascular resistance Establishes hemodynamic baseline
Natriuresis Decreased aldosterone, increased sodium excretion Alters fluid-balance readouts
Reduced GFR acutely Efferent arteriole dilation Affects creatinine and eGFR endpoints
Anti-proteinuric Reduced intraglomerular pressure Confounds albumin-to-creatinine ratio data

For any experiment measuring renal or cardiovascular endpoints, these effects are not background noise, they are active variables. A researcher who introduces a GH secretagogue without first stabilizing ACE inhibitor dosing will be unable to separate peptide-driven changes from ongoing RAAS modulation.


Clinical Evidence Anchoring Lisinopril as the Control Agent

Understanding the evidentiary weight behind lisinopril matters when selecting it as a research control. Its role in ACE inhibitors and research peptides protocols, designing blood-pressure controls around lisinopril and growth-hormone secretagogues, is justified by decades of outcome data, not convention alone.

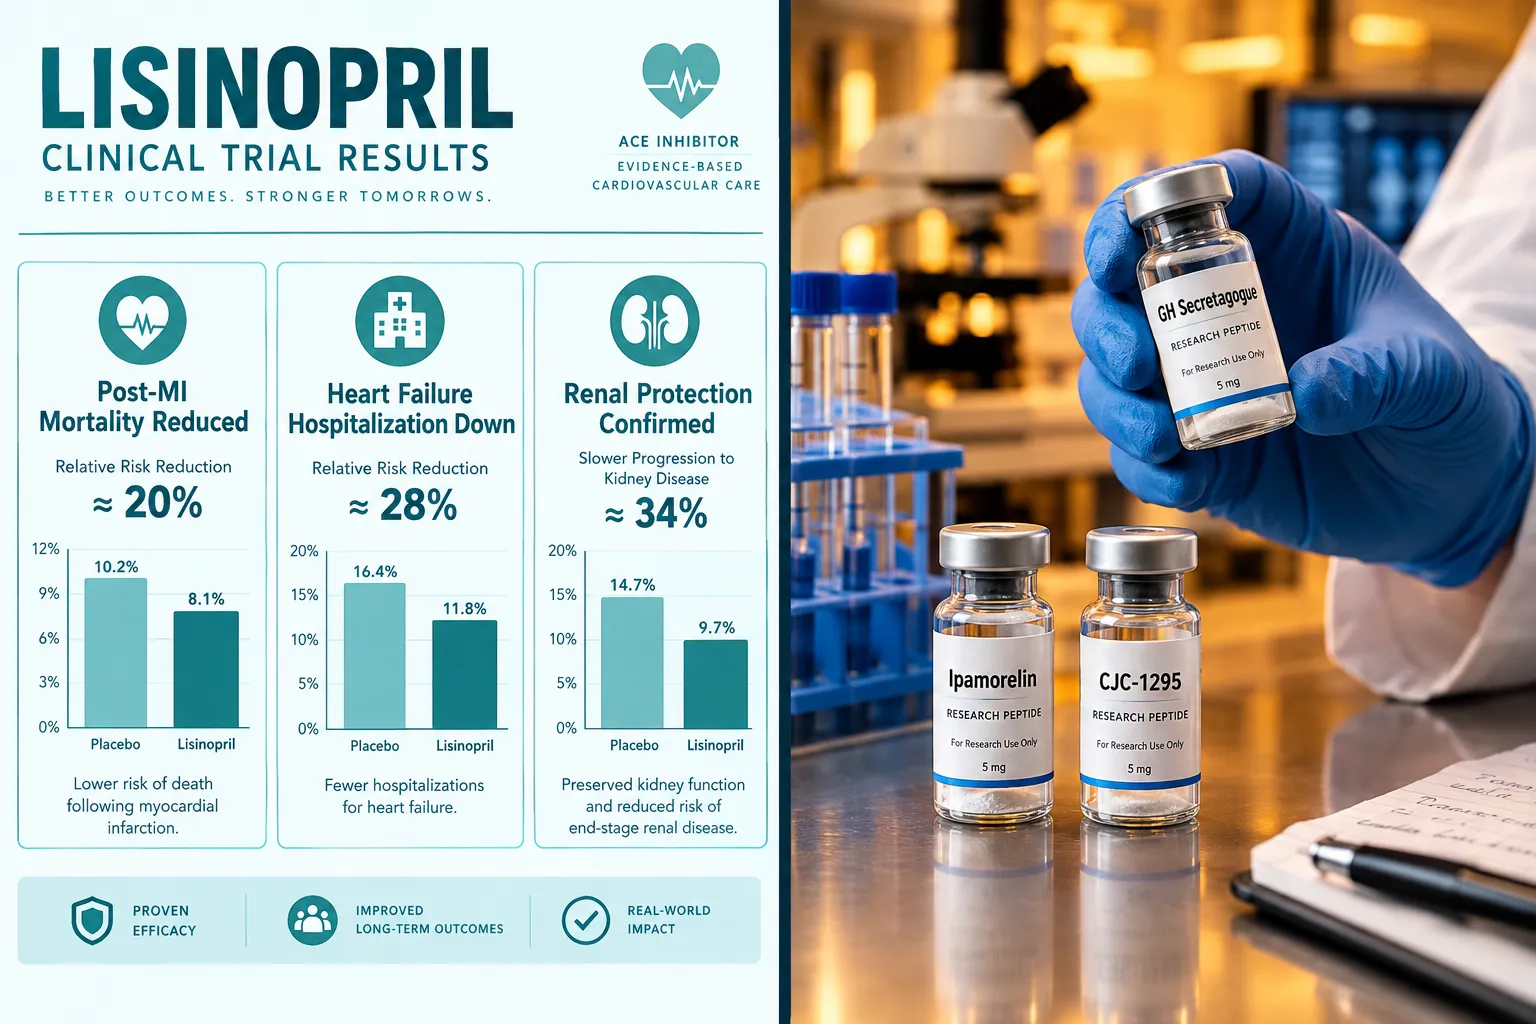
Post-MI data: In the GISSI-3 trial, nearly 19,400 acute myocardial infarction patients were randomized in a factorial design. Lisinopril-treated patients experienced roughly an 11% lower risk of death at six weeks compared with controls (6.4% versus 7.2%), establishing short-term ACE inhibition as a mortality-reducing intervention after cardiac events.

Heart failure dosing: A study in over 3,100 chronic heart-failure patients followed for a median of 46 months found that high-dose lisinopril produced a 12% risk reduction in the combined endpoint of all-cause mortality and hospitalization, and a 24% reduction in heart-failure hospitalizations specifically, compared with low-dose therapy. This supports titrating toward higher target doses when tolerated.

Renal protection: The VA NEPHRON trial enrolled 1,448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratios, and reduced eGFR (30-89.9 mL/min), randomizing them to lisinopril or placebo on a background of losartan. This underscores lisinopril's role in intensive renal-risk management.

Key point: Because lisinopril independently alters urinary albumin excretion and eGFR, any peptide experiment using renal endpoints must document lisinopril dose stability for at least four to six weeks before baseline measurements are taken.

For researchers exploring peptide fundamentals, the Peptides 101 for Research-Use Only Buyers guide provides useful structural and mechanistic context.

Clinical Evidence Anchoring Lisinopril as the Control Agent


GH Secretagogues, Fluid Balance, and Blood-Pressure Risk

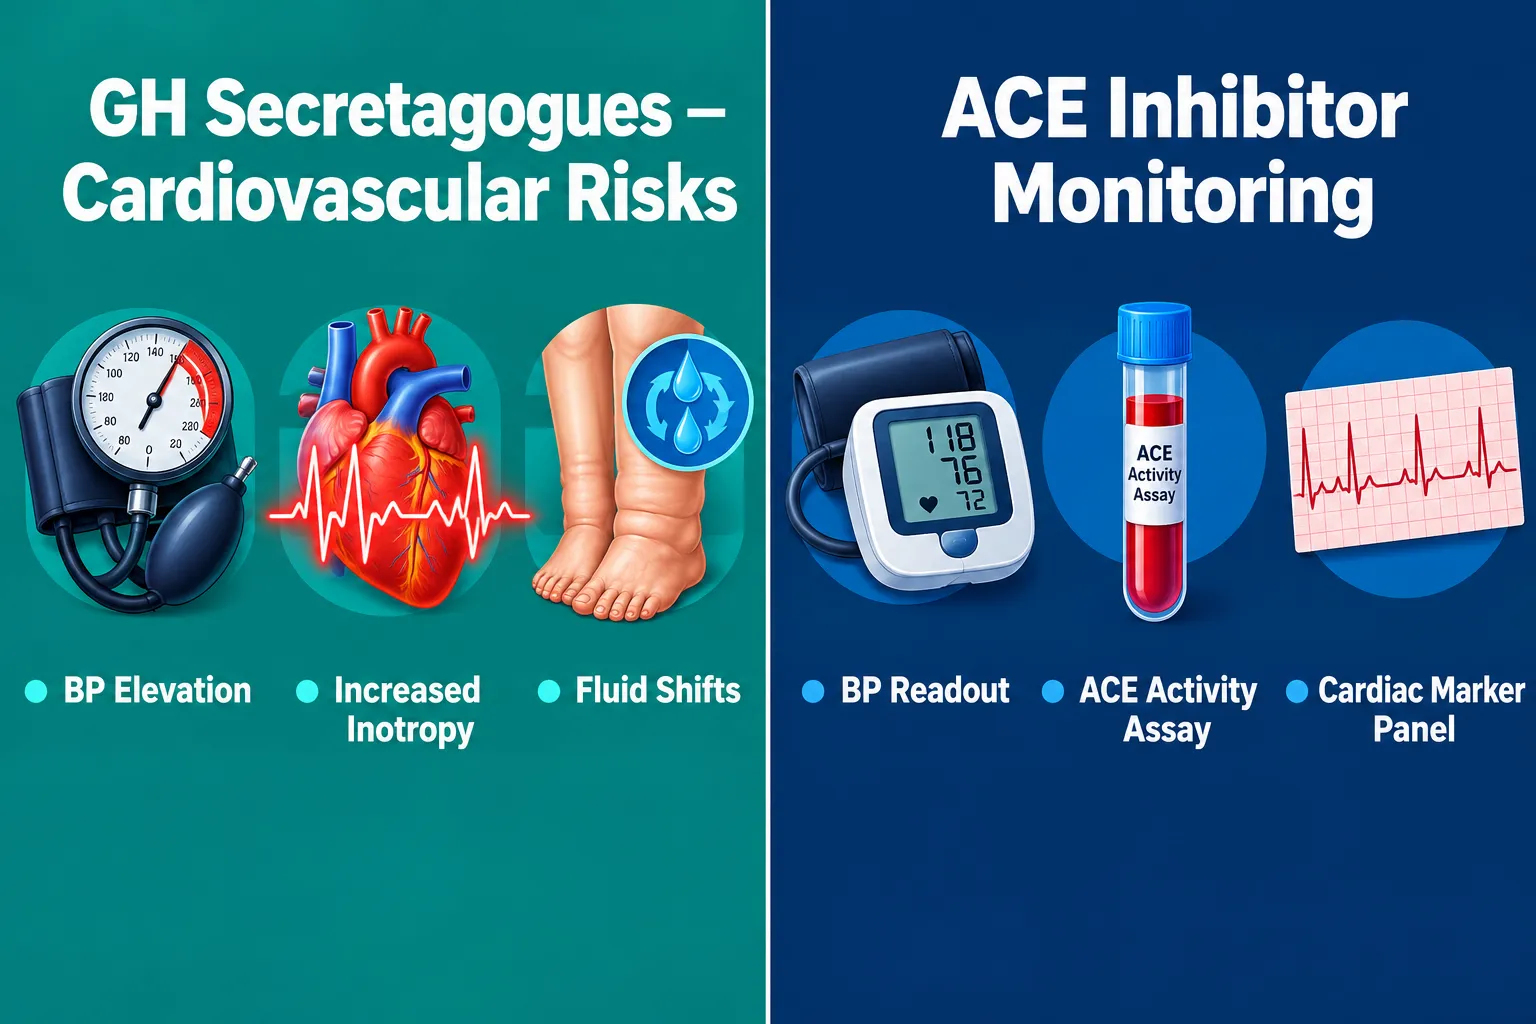
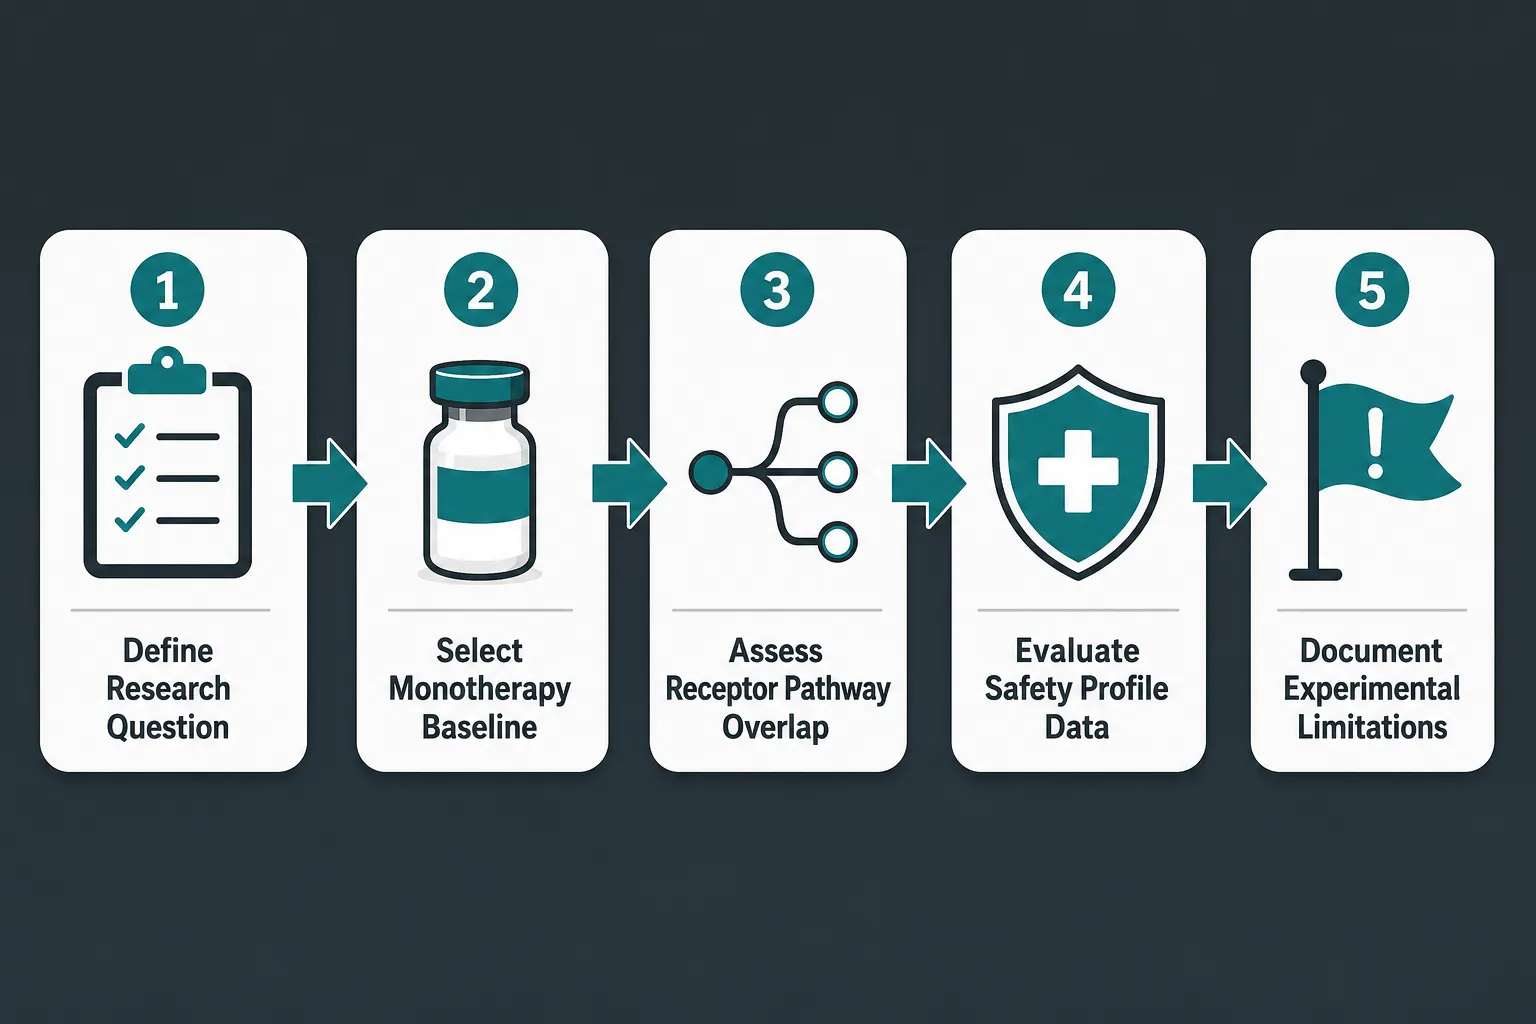
Growth-hormone secretagogues, including ipamorelin, CJC-1295, and tesa, stimulate the pituitary to release growth hormone, which in turn elevates IGF-1. This GH-axis activation carries hemodynamic consequences that directly complicate blood-pressure research design.

The fluid-retention problem: GH promotes sodium and water retention through IGF-1-mediated renal tubular effects. In a subject already on lisinopril, which promotes natriuresis, the opposing forces can mask or amplify fluid shifts, making weight and edema measurements unreliable without careful protocol design.

Blood-pressure uncertainty: No identified human study has directly measured blood-pressure changes attributable to ipamorelin alone. That data gap is critical. Safety reviews in 2026 flag that GH-axis secretagogues can raise blood pressure through both fluid retention and sympathomimetic effects of elevated GH. Specific concern exists at stage 2 hypertension (systolic BP above 160 mmHg), where persistent elevation refractory to standard management is considered a serious adverse event warranting reconsideration of peptide use.

Practical monitoring thresholds:

  • Blood pressure should be checked at every injection-period review
  • Persistent systolic BP above 160 mmHg flags a serious adverse event
  • Patients with cardiovascular disease require cardiologist consultation before GH secretagogue exposure
  • Fluid retention should be tracked via daily weight and ankle circumference measurements

Researchers interested in the IPA Sermorelin stack research protocols will find these monitoring principles directly applicable. For peptide sourcing considerations, the best peptide supplier resource is worth reviewing alongside purity documentation.
GH Secretagogues, Fluid Balance, and Blood-Pressure Risk


Designing a Valid Research Protocol

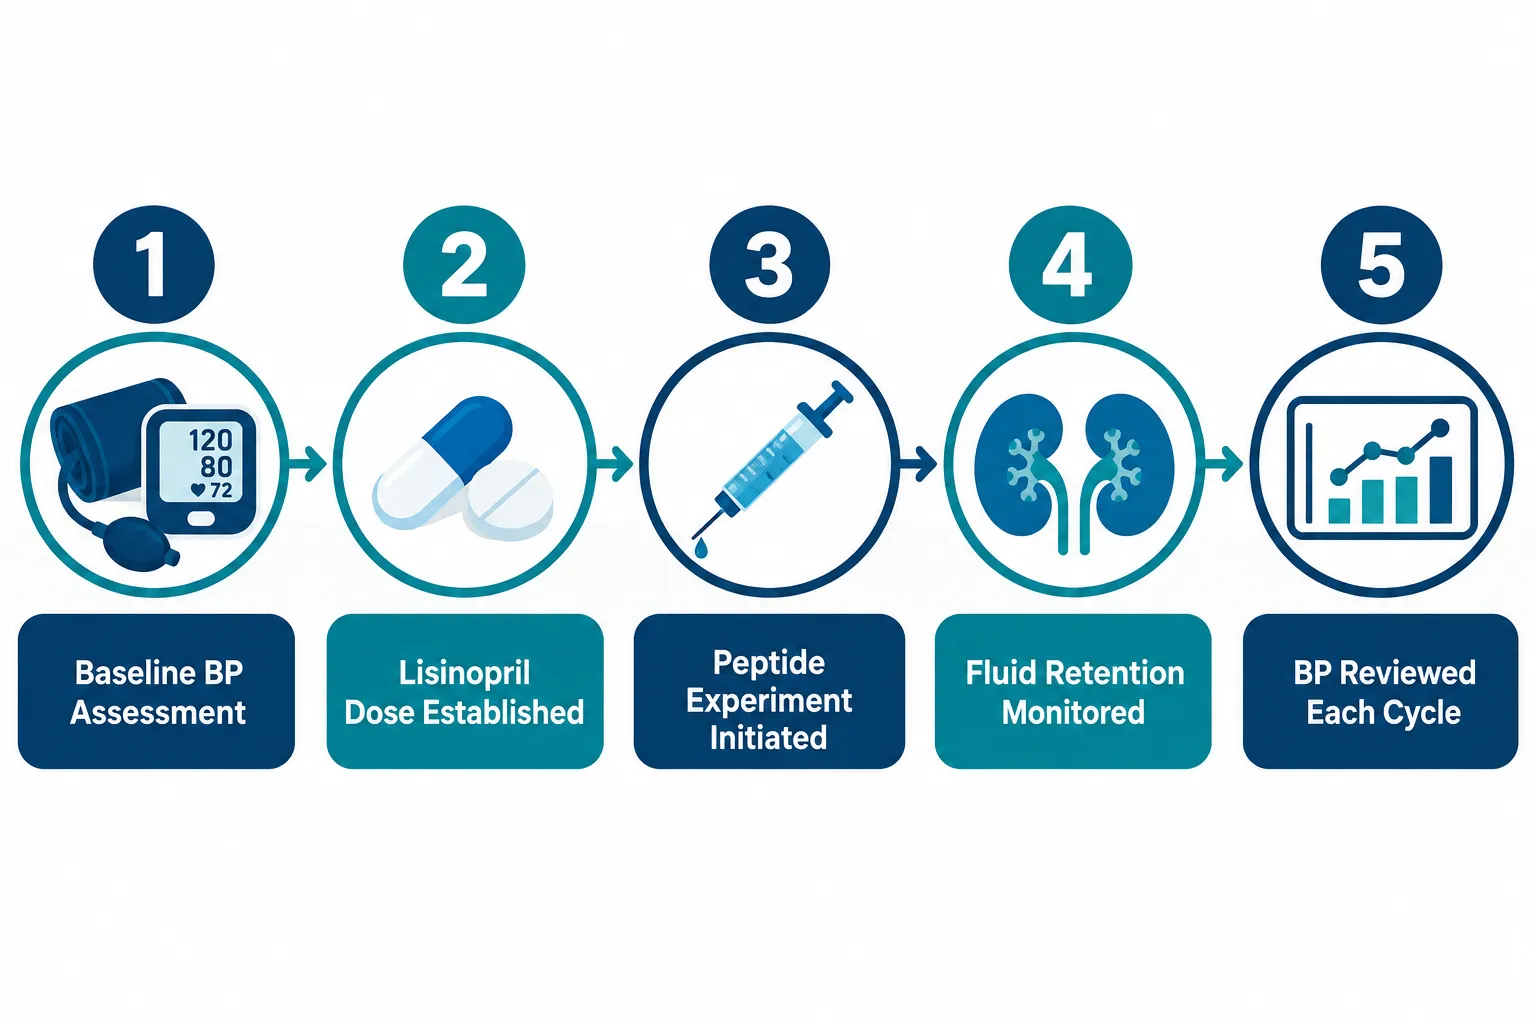
Translating the above into a workable experimental framework requires sequencing interventions carefully. The core principle in ACE inhibitors and research peptides design, blood-pressure controls around lisinopril and growth-hormone secretagogues, is that the ACE inhibitor must be the stable foundation, not an active variable.

Recommended sequencing:

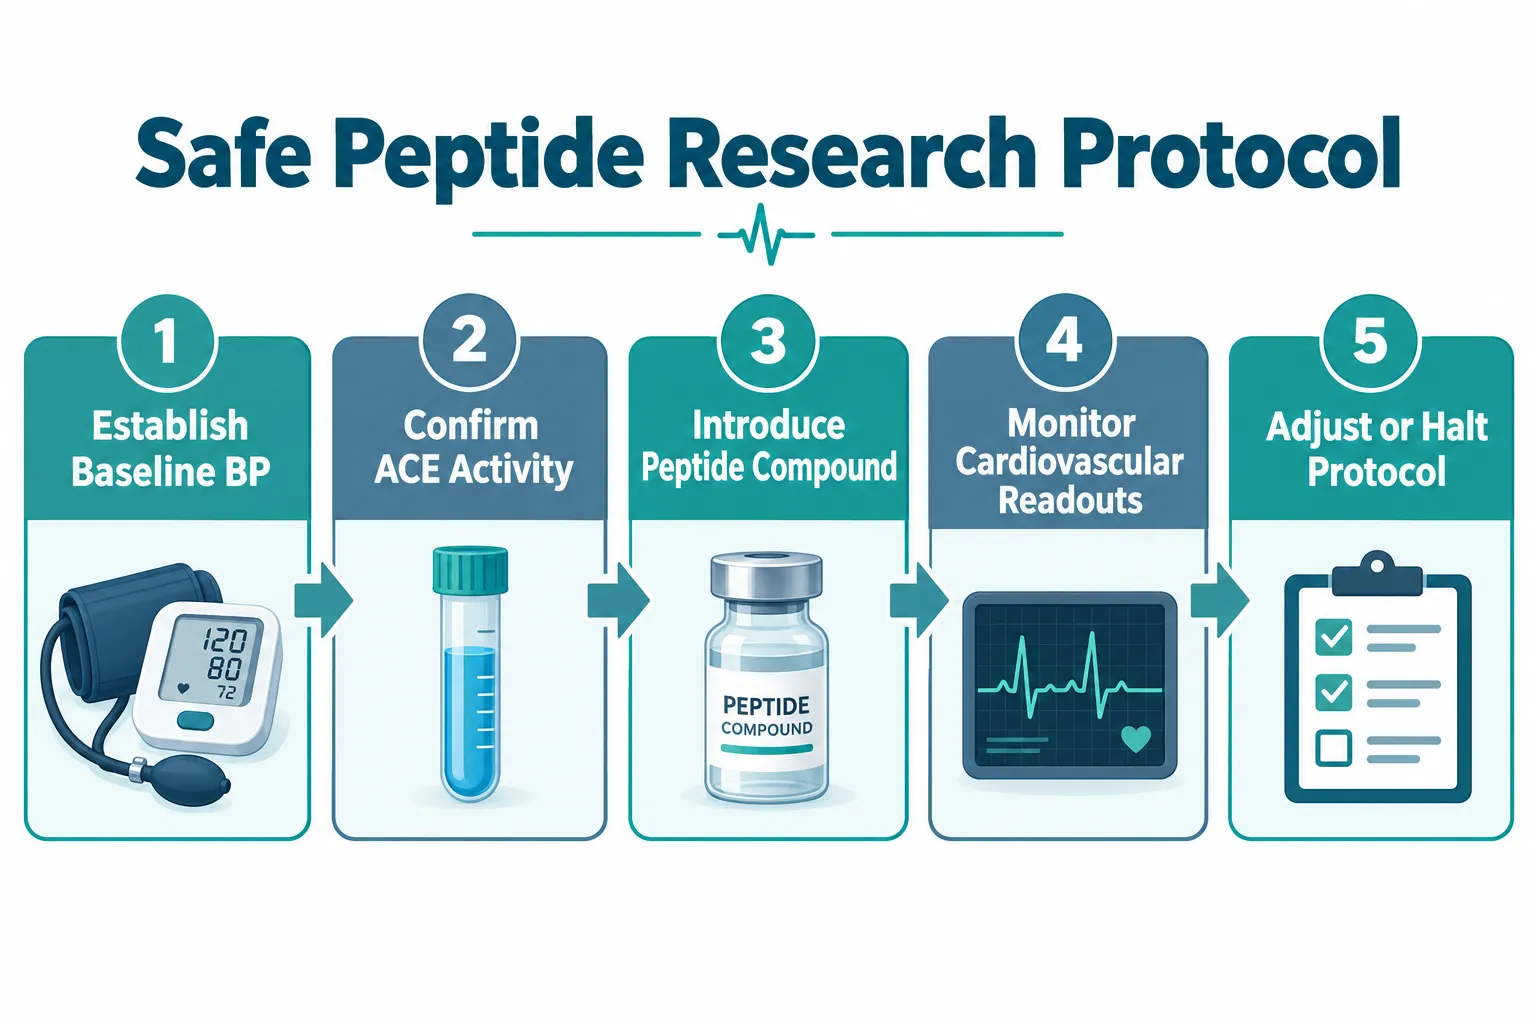
  1. Establish baseline hemodynamics, Record resting BP, eGFR, urinary albumin-to-creatinine ratio, and body weight before any intervention.
  2. Stabilize lisinopril dose, Allow four to six weeks at target dose with three consecutive BP readings within 10 mmHg of each other before proceeding.
  3. Document renal endpoints at steady state, Creatinine, eGFR, and urinary albumin reflect the lisinopril-stabilized baseline, not a moving target.
  4. Introduce the GH secretagogue, Begin ipamorelin, CJC-1295, or tesa at the lowest research dose.
  5. Monitor BP at every injection period, Flag any systolic reading above 160 mmHg as a protocol-defined serious event.
  6. Track fluid balance independently, Daily weight, edema scoring, and sodium intake logs separate peptide-driven fluid shifts from RAAS modulation.

Researchers studying mitochondrial or cytoprotective peptides alongside cardiovascular endpoints may also find the synergy of LL-37 and SS-31 research relevant, as SS-31 has distinct renal mitochondrial effects that interact with RAAS-modulated tissue. Similarly, SS-31 peptide benefits documentation provides useful comparative context when designing multi-peptide cardiovascular studies.

For researchers sourcing MOTS-c or related metabolic peptides alongside GH secretagogues, the MOTS-c peptide category offers additional product and mechanism information.


Conclusion

Designing rigorous blood-pressure controls in peptide research is not optional, it is the difference between interpretable data and noise. Lisinopril's well-characterized effects on RAAS, fluid balance, and renal endpoints make it a logical anchor for cardiovascular control arms, but only when its dose is stabilized before GH secretagogue introduction. Ipamorelin, CJC-1295, and tesa all carry real, if incompletely quantified, risks of fluid retention and blood-pressure elevation that can obscure experimental signals or create genuine safety events.

Actionable next steps for researchers in 2026:

  • Audit existing protocols to confirm lisinopril dose stability windows are documented before baseline renal measurements
  • Add systolic BP above 160 mmHg as a pre-specified serious adverse event criterion in any GH secretagogue study
  • Track fluid balance with daily weight logs, not just clinical BP readings
  • Consult cardiology input for any subject with pre-existing cardiovascular disease before GH-axis peptide exposure
  • Review purity certificates for all research peptides to ensure experimental variables are limited to pharmacology, not contaminant effects
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/ace-inhibitors-and-research-peptides-designing-blood-pressure-controls-around-li.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-27 13:03:392026-09-27 13:03:39ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues
Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts

Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts

September 20, 2026/0 Comments/in Uncategorized/by

Roughly 47% of adults in the United States carry a diagnosis of hypertension, making ACE inhibitors like lisinopril among the most prescribed drugs in modern medicine. That same cardiovascular biology sits at the center of a growing challenge in peptide research: how do labs safely study growth hormone secretagogues (GHS), compounds that measurably alter blood pressure, heart rate, and fluid balance, without losing control of their cardiovascular readouts? Understanding Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts is now a practical necessity for any team working with GHRH analogues, ghrelin mimetics, or related compounds in a controlled setting.

Key Takeaways

  • Lisinopril inhibits ACE, reducing angiotensin II production and lowering blood pressure, a mechanism directly relevant when GH secretagogues cause fluid shifts or BP changes.
  • Growth hormone secretagogues like CJC-1295, Ipamorelin, and MK-677 each carry distinct cardiovascular risk profiles that must be tracked with specific readouts.
  • MK-677 (ibutamoren) has been linked to blood pressure increases and heart failure events in long-term use, prompting FDA warning letters in late 2025.
  • A structured monitoring protocol, baseline BP, ACE activity assay, serial cardiac markers, is essential before and during GHS peptide research.
  • Mitochondrial-targeted peptides such as SS-31 offer a complementary research angle with a favorable cardiovascular safety profile.

ACE Biology and Lisinopril: The Cardiovascular Foundation

ACE Biology and Lisinopril: The Cardiovascular Foundation

The renin-angiotensin-aldosterone system (RAAS) governs blood pressure, fluid volume, and electrolyte balance. At its core sits angiotensin-converting enzyme (ACE), which converts inactive angiotensin I into angiotensin II, a potent vasoconstrictor that also stimulates aldosterone release. Lisinopril binds competitively to the ACE active site, blocking this conversion and producing a cascade of cardiovascular benefits: reduced peripheral resistance, lower blood pressure, and decreased cardiac workload.

In research settings, this mechanism matters for two reasons. First, any peptide compound that independently shifts fluid balance or vascular tone will interact, directly or indirectly, with the same RAAS axis that lisinopril targets. Second, lisinopril itself accumulates bradykinin, which can cause angioedema; this safety signal must be tracked as a background variable in any multi-compound protocol.

Key ACE pathway markers to monitor in research designs:

Readout Why It Matters
Plasma ACE activity Confirms degree of enzymatic inhibition
Angiotensin II levels Tracks downstream vasoconstrictor load
Aldosterone Reflects fluid retention risk
Serum potassium Hyperkalemia risk with ACE inhibition
Bradykinin metabolites Angioedema safety signal

For researchers new to peptide biology, the Peptides 101 for Research-Use Only Buyers: Structure, Mechanisms, and resource provides a useful primer on how different compound classes interact with physiological systems.

Growth Hormone Secretagogues and Cardiovascular Risk: What the Data Show

Growth Hormone Secretagogues and Cardiovascular Risk: What the Data Show

Designing safe peptide research with cardiovascular readouts requires a clear-eyed look at how individual GHS compounds behave in the cardiovascular system. The class is not monolithic, risk profiles differ substantially across agents.

CJC-1295 and GHRH Analogues

CJC-1295 stimulates pulsatile GH release by acting on pituitary GHRH receptors. Elevated GH drives IGF-1 production, and sustained IGF-1 elevation is associated with cardiac hypertrophy and changes in left ventricular geometry in long-term animal studies. Short-term cardiovascular dynamics include modest increases in heart rate and positive inotropic effects. These changes are generally transient but require serial ECG and echocardiographic monitoring in rigorous research designs. A detailed breakdown of pharmacokinetics is available in the CJC-1295 With and Without DAC: A Detailed Mechanism and comparison guide.

Ipamorelin and Ghrelin Mimetics

Ipamorelin is a selective ghrelin receptor agonist with a cleaner selectivity profile than older GHS compounds. Ghrelin itself has demonstrated cardioprotective properties in preclinical models, improving cardiac output and reducing sympathetic tone. However, outcomes data in long-term research remain limited, and the vasodilatory effects of ghrelin-pathway activation can interact unpredictably with ACE inhibitor-induced BP lowering.

MK-677 (Ibutamoren): The Highest-Risk Profile

MK-677 presents the most significant cardiovascular concern in this class. Long-term use has been associated with measurable blood pressure increases, peripheral edema from fluid retention, and, in older research subjects, a higher incidence of heart failure events. FDA warning letters issued in December 2025 specifically flagged ibutamoren-containing products, and 2026 updates reinforced restrictions on its research use. Any protocol using MK-677 alongside an ACE inhibitor must include frequent BP monitoring and renal function panels.

"The interaction between MK-677-driven fluid retention and ACE inhibitor-mediated natriuresis creates a physiologically contested environment that demands close cardiovascular surveillance."

Designing the Protocol: Cardiovascular Readouts for Lisinopril, ACE Pathways, and Growth Hormone Secretagogues Research

Designing the Protocol: Cardiovascular Readouts for Lisinopril, ACE Pathways, and Growth Hormone Secretagogues Research

A rigorous approach to Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts starts before the first compound is introduced. The following framework reflects current best practices for preclinical and in-vitro research designs.

Step 1, Establish Cardiovascular Baseline
Record resting blood pressure, heart rate, and weight. Draw baseline panels: ACE activity, angiotensin II, aldosterone, BNP or NT-proBNP, and a complete metabolic panel. This baseline anchors all subsequent comparisons.

Step 2, Confirm ACE Inhibition Status
If lisinopril is part of the background protocol, verify plasma ACE activity is suppressed to target range before introducing any GHS compound. Residual ACE activity confounds interpretation of peptide-driven BP changes.

Step 3, Introduce GHS Compound With Staged Dosing
Begin at the lowest effective research dose. Refer to established peptide dosing frameworks for compound-specific guidance. Avoid simultaneous introduction of multiple new agents.

Step 4, Serial Cardiovascular Monitoring

  • Blood pressure: every 24-48 hours during acute phase
  • Heart rate and rhythm: ECG at baseline, 72 hours, and weekly
  • IGF-1 levels: weekly, to track GH axis activation
  • BNP/NT-proBNP: bi-weekly as a cardiac stress marker
  • Renal function and electrolytes: weekly (critical with ACE inhibitor co-administration)

Step 5, Integrate Mitochondrial Peptide Data Where Relevant
SS-31, a mitochondria-targeted antioxidant peptide, has shown cardioprotective properties in ischemia-reperfusion models without the BP or fluid-retention liabilities of GHS compounds. Researchers exploring SS-31 mitochondrial research themes may find it a useful comparator arm in cardiovascular peptide studies. Additional mechanistic background is available in the SS-31 mechanism and research overview.

Compounds to avoid combining without extensive monitoring:

  • MK-677 + lisinopril (competing fluid dynamics, hyperkalemia risk)
  • High-dose CJC-1295 + any ACE inhibitor (IGF-1-driven cardiac remodeling risk)
  • Multiple GHS agents simultaneously (additive BP and heart rate effects)

Conclusion

The intersection of lisinopril, ACE pathways, and growth hormone secretagogues is not merely pharmacological, it is a research design challenge with direct safety implications. Labs that approach this space without structured cardiovascular readouts risk misinterpreting compound effects or, worse, missing early signals of cardiac stress.

Actionable next steps for research teams:

  1. Build a standardized cardiovascular baseline panel into every GHS protocol before dosing begins.
  2. Confirm ACE inhibition status when lisinopril is a background agent, and track ACE activity throughout the study.
  3. Treat MK-677 as the highest-risk GHS compound and apply the most rigorous monitoring schedule to any protocol that includes it.
  4. Consider SS-31 as a mechanistically distinct comparator with a favorable cardiovascular profile for studies focused on cardiac or mitochondrial endpoints.
  5. Review the latest FDA guidance from late 2025 and 2026 updates on ibutamoren before finalizing any research involving that compound.

Careful protocol architecture, anchored in ACE biology and supported by serial cardiovascular readouts, is what separates rigorous peptide research from guesswork.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/lisinopril-ace-pathways-and-growth-hormone-secretagogues-designing-safe-peptide.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-20 13:06:092026-09-20 13:06:09Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts
Peptide Drug Interactions: How Research Peptides Interact With Common Medications

Peptide Drug Interactions: How Research Peptides Interact With Common Medications

September 14, 2026/0 Comments/in Uncategorized/by

Fewer than 20% of research peptides currently in active laboratory use have been formally evaluated for drug-drug interactions, a gap that carries real consequences as these compounds move closer to clinical and wellness applications. Understanding Peptide Drug Interactions: How Research Peptides Interact With Common Medications is no longer a niche concern for pharmacologists alone. Researchers, clinicians, and informed consumers need a clear, evidence-informed framework for thinking about these risks in 2026.

Key Takeaways

  • Most research peptides have limited CYP enzyme involvement, but this does not mean they are interaction-free.
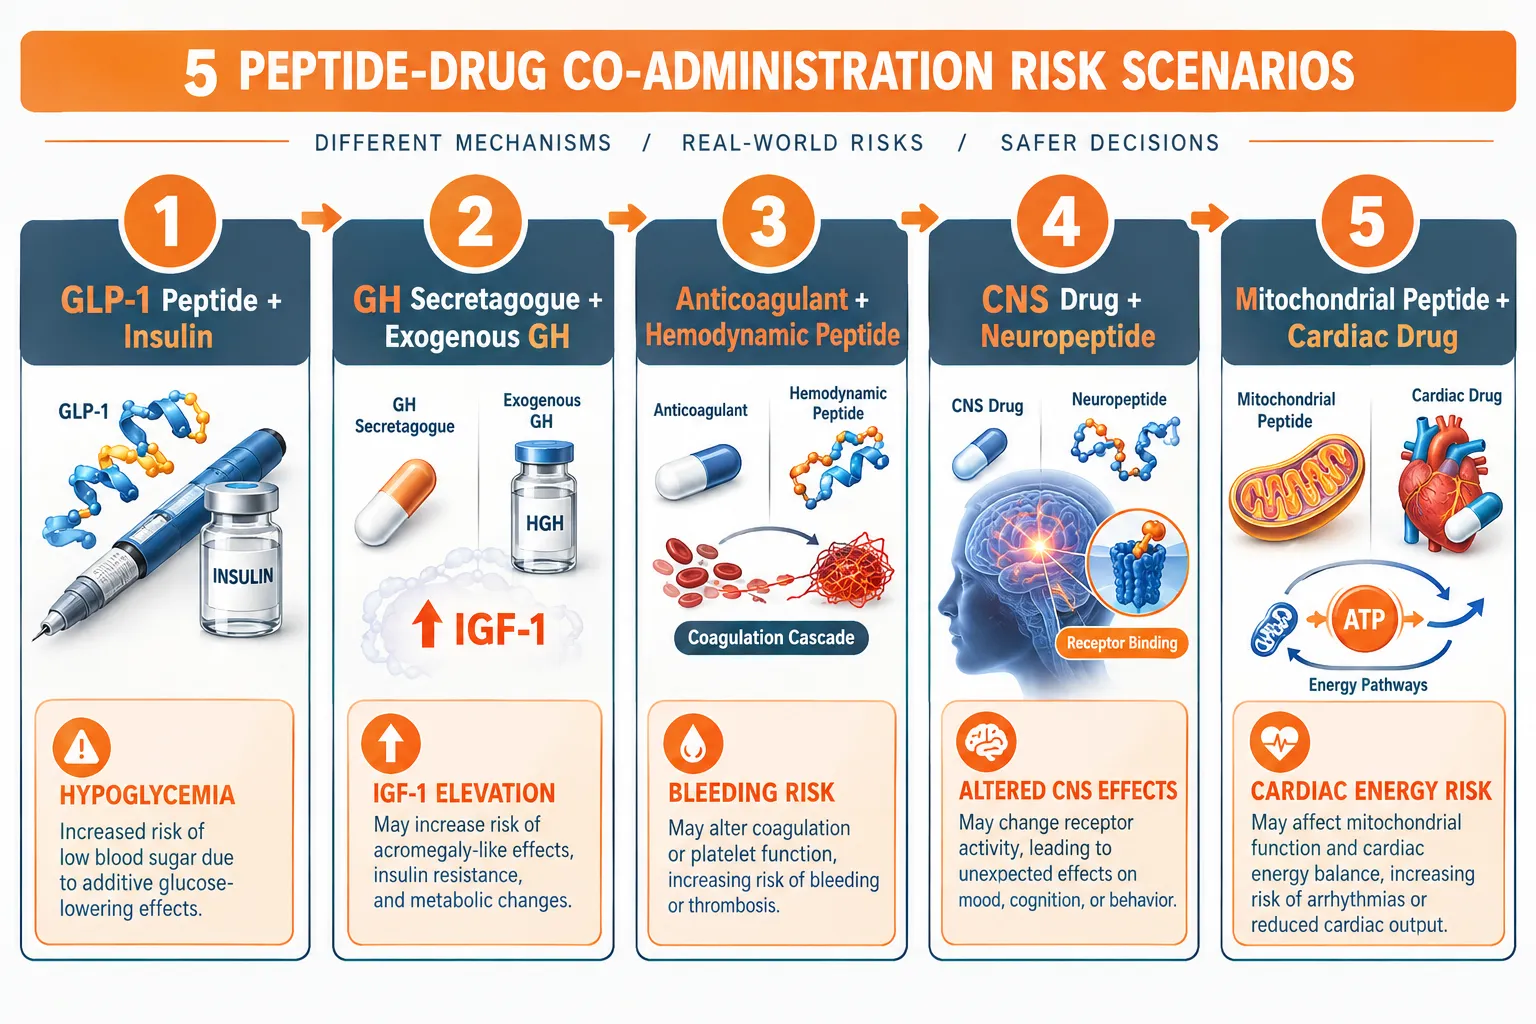
  • GLP-1 type peptides and growth hormone secretagogues carry the highest real-world interaction risk, particularly with insulin and antidiabetic drugs.
  • Peptide size, structural motifs, and route of administration all influence interaction potential.
  • Formal regulatory guidance on peptide drug interactions remains incomplete as of mid-2026.
  • Researchers and clinicians should apply a precautionary framework, especially in patients on anticoagulants, cardiovascular drugs, or CNS medications.

Why Peptide Drug Interactions Are Poorly Understood

Why Peptide Drug Interactions Are Poorly Understood

The science of peptide pharmacokinetics has advanced rapidly, but the field of peptide-drug interactions has not kept pace. A 2025 clinical review confirmed that formal guidance on this topic is still largely absent, leaving researchers to extrapolate from limited mechanistic data.

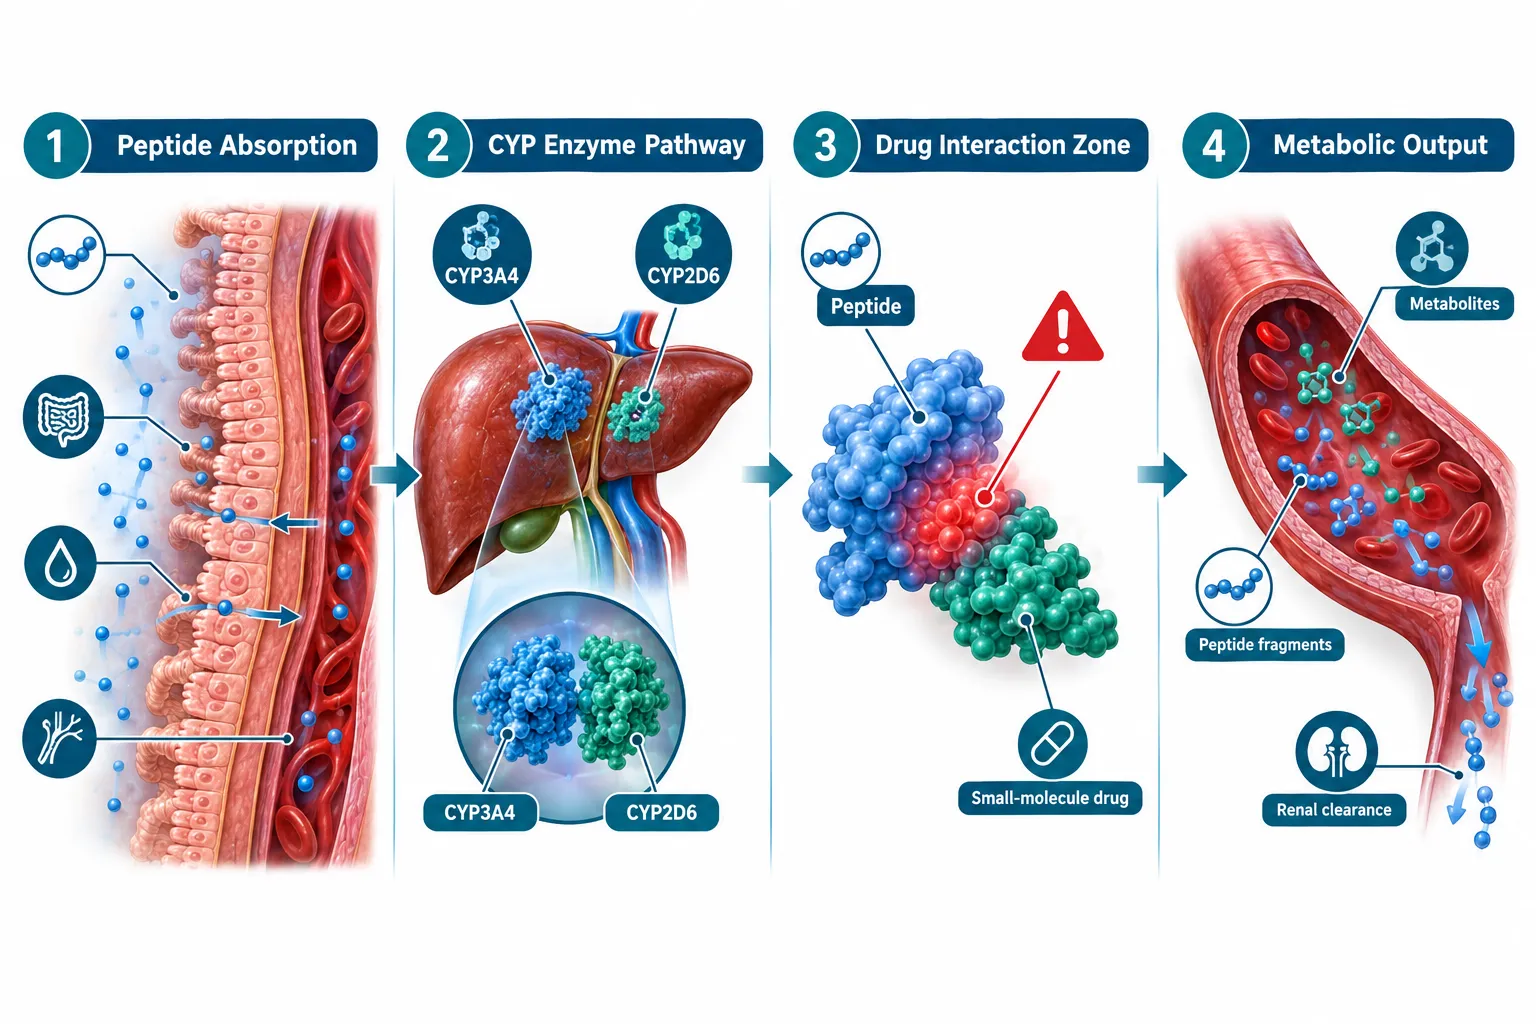
One reason for the knowledge gap is structural. Unlike small-molecule drugs, most peptides are broken down by proteases rather than by cytochrome P450 (CYP) liver enzymes. This means the classic drug interaction framework, built around CYP3A4, CYP2D6, and related pathways, does not map cleanly onto peptide pharmacology.

However, minimal CYP involvement is not the same as zero interaction risk. Peptides can still alter drug behavior through:

  • Receptor-level competition or synergy
  • Hormonal and metabolic downstream effects
  • Changes in gastric emptying, fluid balance, or hemodynamics
  • Indirect modulation of enzyme expression over time

A humanized mouse model published in 2025 confirmed low CYP-mediated drug-drug interaction (DDI) risk for larger peptides, and a 2024-2025 pharmacological interaction matrix analysis found that risk correlates with peptide size and the presence of non-peptide motifs. Smaller peptides with synthetic or hybrid structures carry meaningfully higher interaction potential.

For researchers exploring polypeptide peptides in cardiometabolic models, understanding this distinction is foundational.

"The absence of CYP involvement creates a false sense of safety. The real interaction risks for research peptides lie elsewhere, in hormonal cascades, receptor overlap, and hemodynamic shifts."

Peptide Drug Interactions: How Research Peptides Interact With Common Medications in Practice

Peptide Drug Interactions: How Research Peptides Interact With Common Medications in Practice

The most clinically significant interaction scenarios involve four major drug categories. Each presents a distinct mechanism and risk profile.

Insulin and Antidiabetic Drugs

GLP-1 peptides and growth hormone secretagogues can substantially amplify the glucose-lowering effects of insulin, metformin, and sulfonylureas. Co-administration creates a compounding hypoglycemia risk that is not always predictable from either agent alone. This is one of the best-documented interaction categories in the research peptide space.

Growth Hormone and IGF-1 Pathways

Peptides that stimulate endogenous growth hormone release, including several widely studied secretagogues, should generally not be combined with exogenous growth hormone. The additive effect on IGF-1 elevation carries metabolic and cardiovascular consequences. This combination is broadly flagged as one to avoid in research protocols.

For context on how one mitochondrial-targeted peptide is evaluated in isolation, see SS-31 10mg research peptide considerations.

Anticoagulants and Cardiovascular Medications

Even when CYP pathways are uninvolved, peptides that alter hemodynamics, endothelial function, or fluid balance can change the effective exposure of anticoagulants like warfarin or direct oral anticoagulants (DOACs). This is a pharmacodynamic interaction rather than a pharmacokinetic one, and it is frequently overlooked.

Interaction Risk Summary by Drug Class

Drug Class Interaction Type Risk Level
Insulin / Antidiabetics Pharmacodynamic (additive) High
Exogenous Growth Hormone Hormonal cascade (additive) High
Anticoagulants / CVD drugs Hemodynamic / fluid balance Moderate-High
CNS Medications Receptor-level overlap Moderate (context-dependent)

CNS and Neurological Drugs

Neuropeptides and peptides with CNS activity, including some under active Semax research protocols, may interact with antidepressants, anxiolytics, or antiepileptics through receptor-level mechanisms. The interaction data here is sparse, and safety advocacy groups flagged in June 2026 that interaction risk for wellness and "PCAC" peptides remains largely unknown.

Regulatory Context and What It Means for Researchers

Regulatory Context and What It Means for Researchers

The regulatory landscape shifted meaningfully in the first half of 2026. In March and April 2026, the FDA took enforcement action against sellers of "research-use-only" GLP-1 analog peptides, signaling a harder line on compounds that blur the boundary between research chemicals and unapproved therapeutics. Then, in July 2026, a regulatory framework update confirmed that while CYP involvement for most peptides remains minimal, caution is warranted in high-risk patient populations.

On July 28, 2026, the FDA also shifted its scientific position on generic peptide products, a move with downstream implications for how interaction data will be required and evaluated going forward.

For researchers sourcing compounds, working with lab tested peptides that carry documented purity profiles is a baseline requirement. Impurities and degradation products can introduce interaction variables that are entirely separate from the peptide's intended pharmacology.

Researchers studying endocrine-active compounds should also review how peptides interface with receptor biology, as covered in the analysis of peptides and polypeptides in endocrine pharmacology.

Practical precautions for 2026 research contexts:

  • Document all co-administered agents before initiating any peptide protocol
  • Apply heightened scrutiny when subjects are on insulin, anticoagulants, or cardiovascular drugs
  • Treat absence of CYP data as absence of evidence, not evidence of absence
  • Monitor for pharmacodynamic interactions even when pharmacokinetic data is reassuring
  • Consult updated FDA guidance before working with GLP-1 class analogs

Conclusion

Peptide Drug Interactions: How Research Peptides Interact With Common Medications represent a genuine and underappreciated safety domain. The low CYP involvement of most peptides does not eliminate interaction risk, it simply shifts where that risk lives. The highest-priority concerns in 2026 involve GLP-1 and growth hormone-related peptides combined with insulin or exogenous GH, anticoagulants in patients with hemodynamic-active peptides, and CNS drugs paired with neuropeptides.

Actionable next steps for researchers and practitioners:

  1. Build a complete co-medication profile before any peptide protocol begins.
  2. Prioritize compounds with documented purity and available pharmacological data.
  3. Monitor the FDA's evolving position on peptide classification, particularly for GLP-1 analogs.
  4. Apply pharmacodynamic interaction logic even when pharmacokinetic data is absent.
  5. Revisit interaction assumptions regularly, the evidence base is moving fast in 2026.

The field is advancing. Staying ahead of the interaction risk curve is not optional, it is foundational to responsible research practice.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptide-drug-interactions-how-research-peptides-interact-with-common-medications-1.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:06:172026-09-14 13:06:17Peptide Drug Interactions: How Research Peptides Interact With Common Medications
Tesamorelin vs Ipamorelin in Body Composition Research: How Labs Model GH Pulsatility, Lean Mass, and Recovery With Different Secretagogues

Tesamorelin vs Ipamorelin in Body Composition Research: How Labs Model GH Pulsatility, Lean Mass, and Recovery With Different Secretagogues

September 6, 2026/0 Comments/in Uncategorized/by

Only one growth hormone secretagogue has completed large, randomized, double-blind, placebo-controlled trials enrolling more than 800 subjects and earned FDA approval for a body-composition endpoint. That distinction belongs to tesa. Yet ipamorelin continues to attract significant research interest in 2026 for its clean receptor selectivity and its ability to mimic endogenous GH pulse architecture. Understanding the practical differences between these two peptides requires looking well beyond basic GH secretion, into visceral fat phenotypes, lean mass trajectories, hepatic biomarkers, and recovery kinetics. This article examines Tesamorelin vs Ipamorelin in Body Composition Research: How Labs Model GH Pulsatility, Lean Mass, and Recovery With Different Secretagogues to help researchers select the right tool for the right experimental question.

Key Takeaways

  • Tesamorelin is the only GH secretagogue with robust RCT data showing measurable decreases in visceral fat and increases in lean body mass.
  • Ipamorelin produces sharp, pulsatile GH spikes that closely resemble endogenous nocturnal GH bursts, making it a useful tool for modeling GH pulse architecture.
  • No head-to-head clinical trial comparing tesa and ipamorelin for body-composition endpoints currently exists.
  • Ipamorelin's body-composition evidence is classified as Tier D, zero randomized controlled trials measuring lean mass, fat mass, or strength outcomes.
  • The practical research hierarchy in 2026 positions tesa as the gold standard for visceral fat and recomposition models, while ipamorelin serves primarily as a pulsatility and recovery research tool.

Receptor Mechanisms and GH Pulse Profiles

Receptor Mechanisms and GH Pulse Profiles

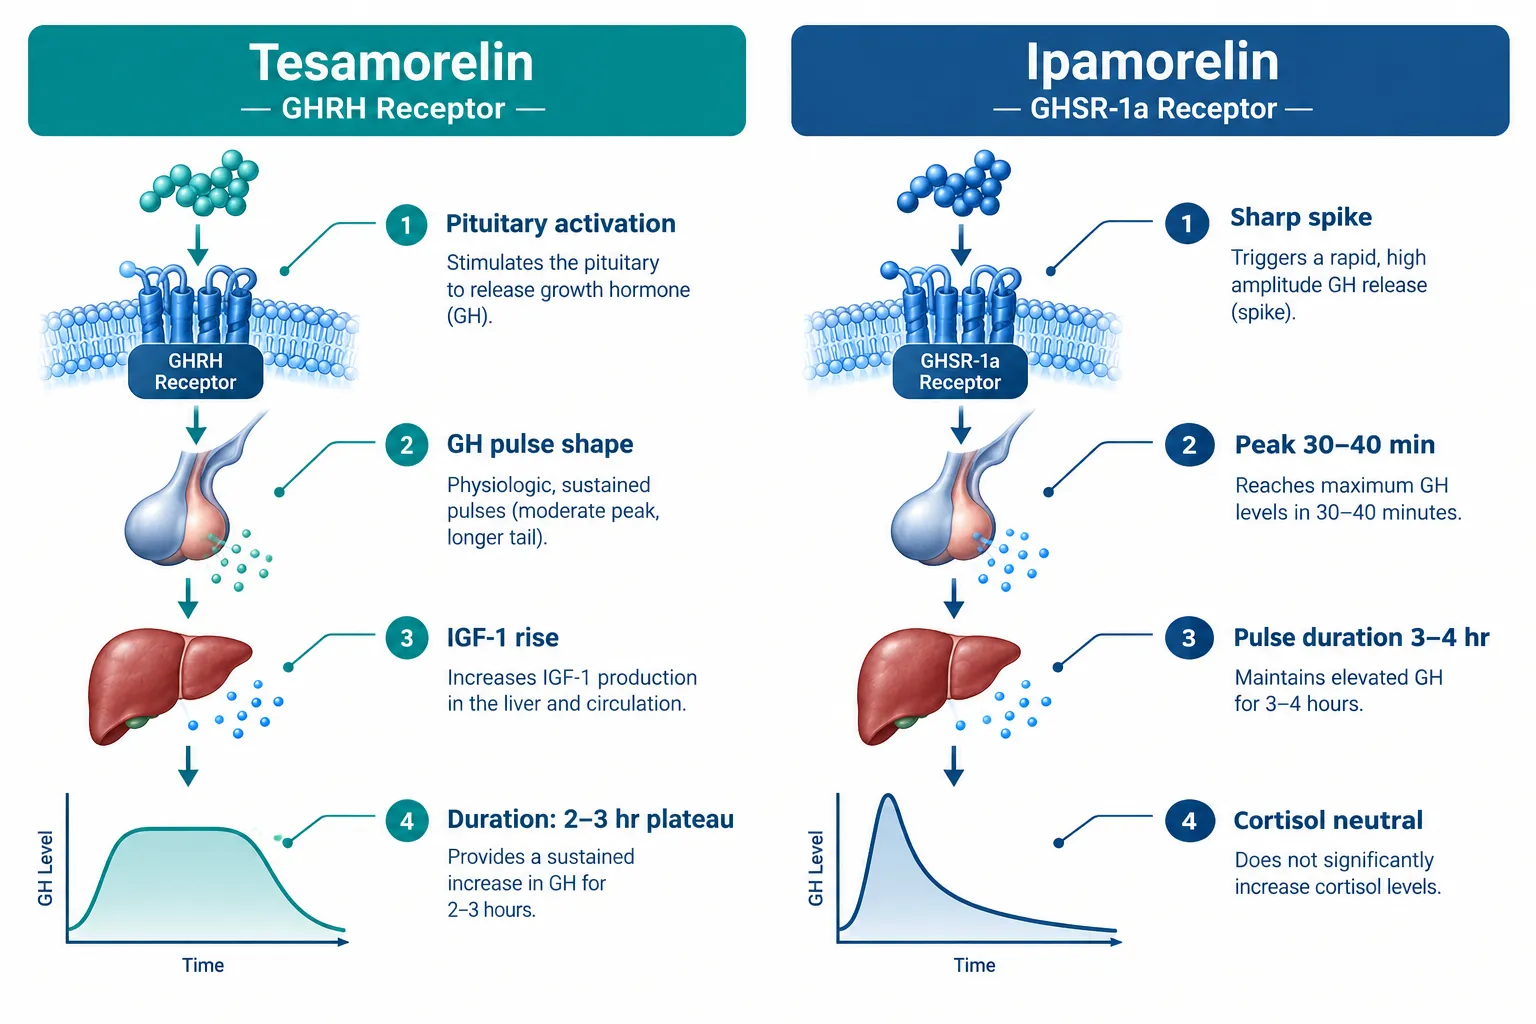
Tesamorelin is a stabilized analogue of endogenous growth hormone-releasing hormone (GHRH). It binds directly to the pituitary GHRH receptor, stimulating a sustained, relatively broad GH release pattern, onset within approximately 30 minutes, followed by a 2-to-3-hour elevated plateau. This profile generates robust IGF-1 elevation and supports the downstream anabolic and lipolytic signaling that underpins its body-composition effects.

Ipamorelin operates through an entirely different receptor. As a selective ghrelin receptor (GHSR-1a) agonist, it produces sharp, spike-like GH pulses with peak concentrations occurring roughly 30 to 40 minutes post-injection and a pulse duration of approximately 3 to 4 hours. These spike-like pulses more closely resemble the nocturnal GH bursts that occur naturally during slow-wave sleep, making ipamorelin particularly attractive for research models focused on physiological GH pulsatility.

The key mechanistic distinction:

Feature Tesamorelin Ipamorelin
Receptor target GHRH receptor GHSR-1a (ghrelin receptor)
GH release pattern Broad plateau, 2-3 hr Sharp spike, 3-4 hr pulse
IGF-1 elevation Robust, well-documented Short-term, less characterized
Cortisol/prolactin impact Minimal Minimal in short-term studies
Regulatory status FDA-approved (Egrifta) Investigational only

For researchers exploring Tesamorelin vs Ipamorelin at the mechanistic level, these receptor differences translate directly into different experimental designs and measurable endpoints.

Tesamorelin vs Ipamorelin in Body Composition Research: Evidence Quality and Endpoint Data

Tesamorelin vs Ipamorelin in Body Composition Research: Evidence Quality and Endpoint Data

The evidence gap between these two peptides is substantial and should anchor every research decision.

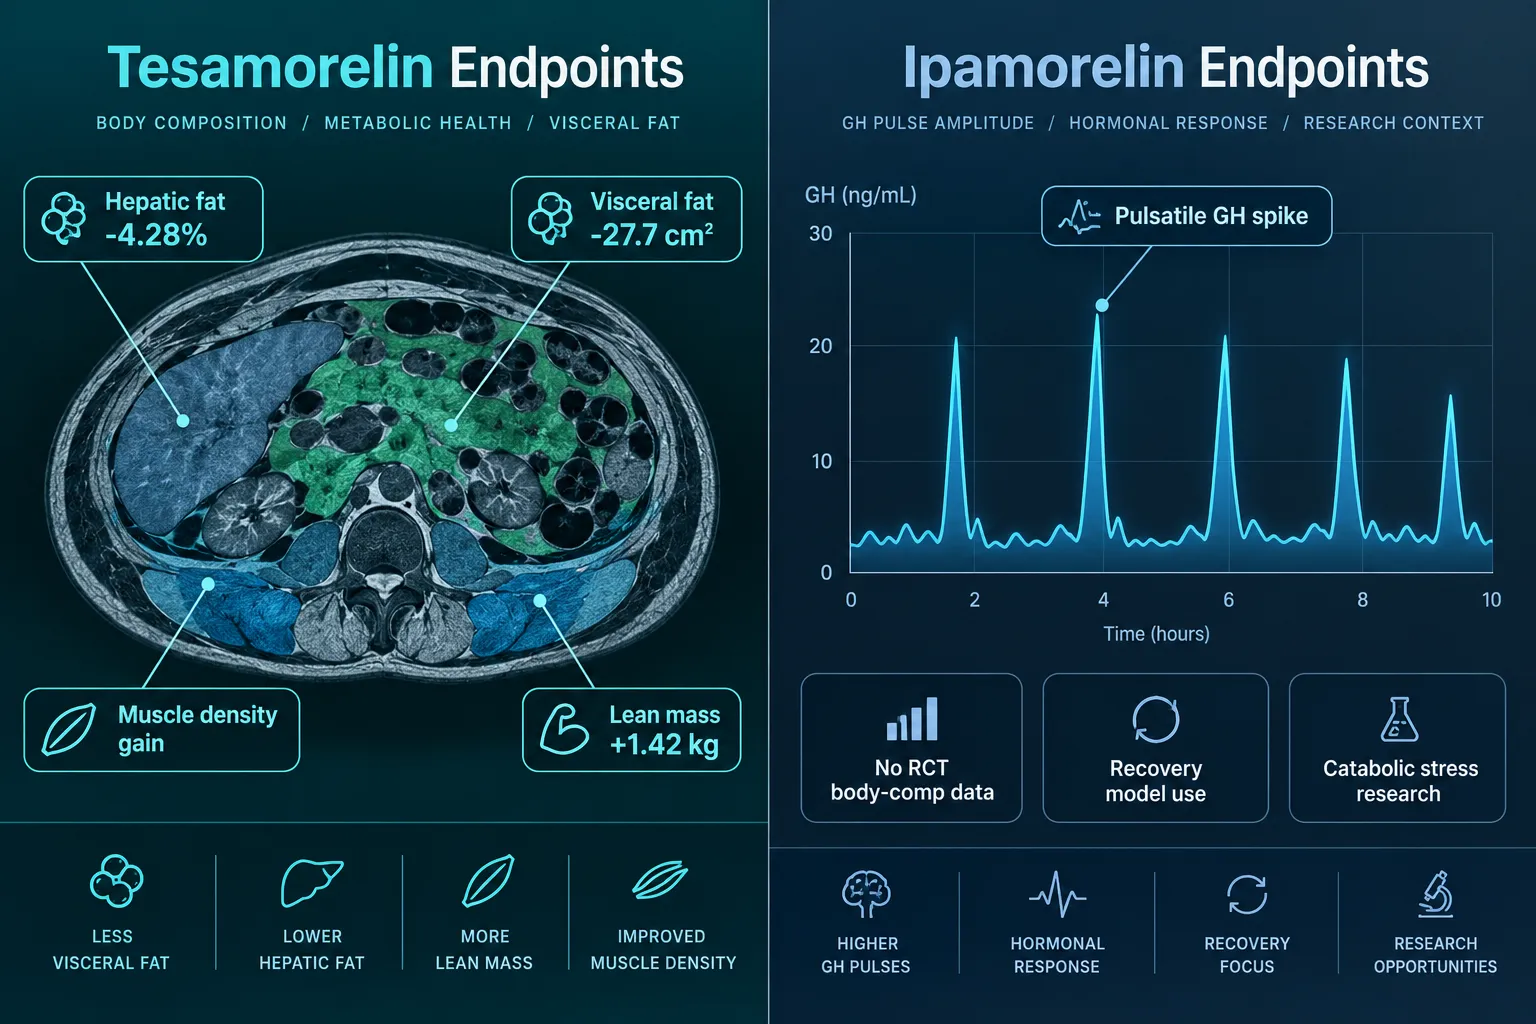
Tesamorelin's body-composition dataset is the strongest among all GH secretagogues. A 2026 meta-analysis of randomized controlled trials in HIV-associated lipodystrophy quantified the following mean effects:

  • Visceral adipose tissue: -27.71 cm²
  • Trunk fat: -1.18 kg
  • Lean body mass: +1.42 kg
  • Hepatic fat percentage: -4.28%
  • Waist circumference: -1.61 cm

Phase III trial data further show 15 to 18% reductions in visceral adipose tissue over 6 to 12 months, alongside increases in muscle density of approximately 1.6 to 4.9 Hounsfield units and muscle cross-sectional area gains of 0.4 to 1.1 cm². These findings establish tesa not as a general weight-loss agent, but as a targeted recomposition tool, reducing deep abdominal and hepatic fat while preserving or building lean mass. Researchers interested in the broader tesa benefits profile will find this dataset particularly relevant to experimental design.

Ipamorelin's body-composition dataset is, by contrast, essentially nonexistent at the human trial level. Current research classifications assign it a Tier D evidence rating for body-composition endpoints, meaning zero randomized controlled trials have measured lean mass, fat mass, or strength outcomes. Human data are limited to pharmacokinetic and pharmacodynamic studies and a discontinued Phase II trial for postoperative ileus.

The most recent in-vivo work highlighted in 2026 comes from a ferret chemotherapy model, where ipamorelin at 1 to 3 mg/kg reduced cisplatin-induced body-weight loss by approximately 24% during the delayed phase (48 to 72 hours). While this suggests a potential role in supporting weight maintenance during catabolic stress, these are preclinical findings that have not yet been translated into human recovery protocols.

"The trade-off is essentially clinical validation versus selectivity: tesa offers trial-based improvements in visceral fat and lean mass; ipamorelin offers the cleanest GH-axis selectivity with minimal downstream hormonal disruption."

For labs working with multi-peptide formulations, resources on Tesamorelin CJC-1295 Ipamorelin 12mg blend protocols provide additional context on how these agents are combined in research settings.

Tesamorelin vs Ipamorelin in Body Composition Research: Lab Modeling Strategies for Pulsatility, Lean Mass, and Recovery

Tesamorelin vs Ipamorelin in Body Composition Research: Lab Modeling Strategies for Pulsatility, Lean Mass, and Recovery

Because no head-to-head clinical trial exists, labs must make deliberate modeling choices based on the endpoint they are investigating.

When to model with tesa:

  • Deep abdominal and visceral fat phenotypes
  • NAFLD-like hepatic steatosis endpoints
  • Recomposition paradigms requiring simultaneous fat loss and lean mass preservation
  • IGF-1 and hepatic fat biomarker panels
  • Studies combining GH secretagogues with GLP-1 analogs to preserve lean body mass during aggressive fat reduction

Researchers can consult the tesa dosage chart for reference ranges used in published protocols, and the tesa side effects profile, predominantly mild injection-site reactions and transient arthralgia, should be incorporated into study safety monitoring plans.

When to model with ipamorelin:

  • GH pulse amplitude and frequency studies
  • Sleep-related GH secretion models
  • Short-window GH-axis activation with minimal cortisol, prolactin, or ACTH interference
  • Post-operative or chemotherapy-induced catabolism models (preclinical)
  • Recovery kinetics after intense training stimuli

For labs exploring combined secretagogue approaches, the IPA Sermorelin stack research page offers relevant protocol context. Additionally, researchers interested in the pharmacokinetic differences between GHRH analogues should review CJC-1295 with and without DAC as a complementary reference for understanding how half-life modifications alter pulse modeling.

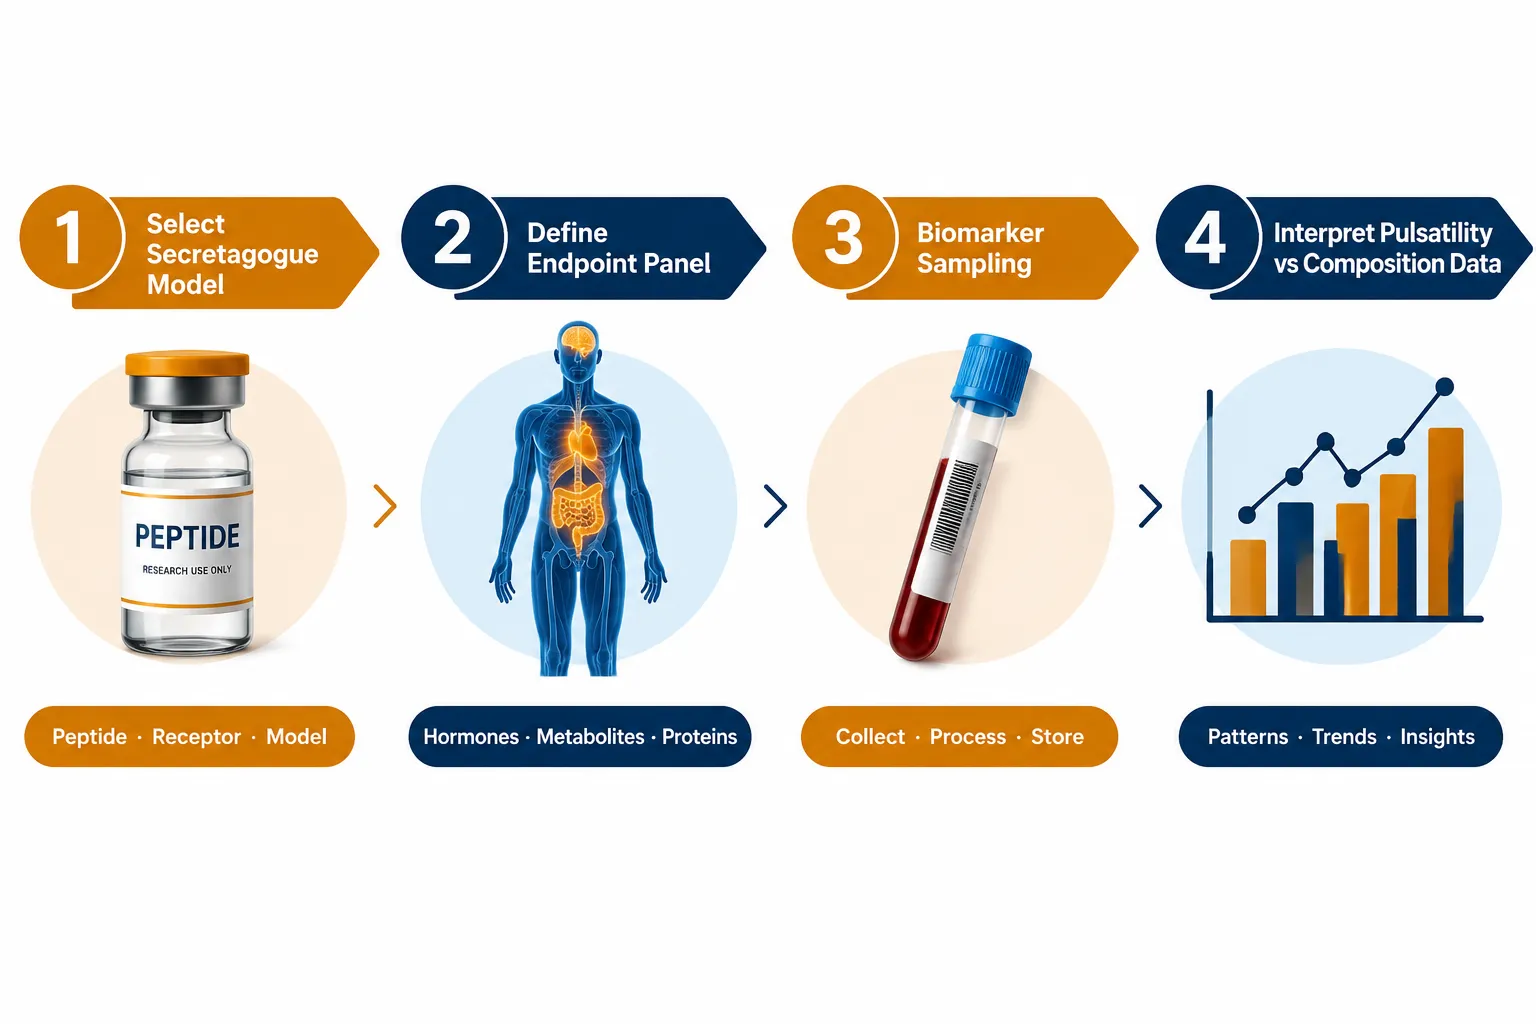
Biomarker panel recommendations by agent:

  • Tesamorelin studies: IGF-1, visceral adipose tissue by CT or MRI, hepatic fat fraction, trunk and limb fat by DEXA, muscle cross-sectional area, fasting glucose, lipid panel
  • Ipamorelin studies: GH pulse amplitude and frequency (serial sampling), IGF-1 (short-term), cortisol, prolactin, ACTH (to confirm selectivity), body weight in catabolic models

Conclusion

The research landscape in 2026 is clear on one point: tesa and ipamorelin are not interchangeable tools. Tesamorelin is the evidence leader for body-composition research, the only GHRH-pathway peptide with meta-analytic RCT data demonstrating measurable reductions in visceral fat, hepatic fat, and trunk fat alongside lean mass gains. Ipamorelin's value lies in its receptor selectivity and its ability to model physiological GH pulsatility without significant hormonal crosstalk, but its body-composition effects remain speculative pending controlled human trials.

Actionable next steps for research teams:

  1. Define your primary endpoint first, visceral fat reduction and lean mass require tesa; GH pulse modeling and recovery kinetics favor ipamorelin.
  2. Build biomarker panels that match the mechanism: IGF-1 and imaging endpoints for tesa; serial GH sampling and selectivity markers for ipamorelin.
  3. Review published tesa RCT data as the baseline reference for any GH secretagogue body-composition study.
  4. Treat ipamorelin findings as hypothesis-generating until human efficacy trials are completed.
  5. Ensure peptide purity and documentation before initiating any protocol, certificate-of-analysis verification is non-negotiable for reproducible results.
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/tesa-vs-ipamorelin-in-body-composition-research-how-labs-model-gh-pulsati.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-06 13:03:542026-09-06 13:03:54Tesamorelin vs Ipamorelin in Body Composition Research: How Labs Model GH Pulsatility, Lean Mass, and Recovery With Different Secretagogues
Peptides in Basic Cell Biology: How GLP-3, GLP-2-T, and Growth Hormone Secretagogues Interact With Animal and Plant Cells

Peptides in Basic Cell Biology: How GLP-3, GLP-2-T, and Growth Hormone Secretagogues Interact With Animal and Plant Cells

September 3, 2026/0 Comments/in Uncategorized/by

Fewer than five years ago, the concept of a single peptide activating three distinct hormone receptors simultaneously existed only in theoretical pharmacology. Today, the study of peptides in basic cell biology, how GLP-3, GLP-2-T, and growth hormone secretagogues interact with animal and plant cells, sits at the center of metabolic research, driving some of the most consequential findings in endocrine science and preclinical investigation.

Key Takeaways

  • GLP-3 is not a naturally occurring hormone but an informal label for synthetic triple agonist peptides such as retatrutide, which simultaneously activates GLP-1R, GIPR, and glucagon receptors in animal cells.
  • GLP-2-T refers to tirzepatide-class dual incretin peptides that target GLP-1R and GIPR, reshaping signaling in pancreatic, hepatic, and neuronal cell populations.
  • Growth hormone secretagogues act through the GHSR1a receptor, a seven-transmembrane GPCR found in pituitary, hypothalamic, and other vertebrate tissues.
  • None of these receptor systems, GLP-1R, GIPR, GCGR, GLP-2R, or GHSR1a, have been identified in plant cell genomes, making their interaction with plant cells non-canonical and outside current mainstream research.
  • All three peptide classes are currently classified as research-use-only compounds, applied in controlled in-vitro and preclinical animal cell studies.

Understanding GLP-3 and GLP-2-T in Animal Cell Signaling

Understanding GLP-3 and GLP-2-T in Animal Cell Signaling

The label "GLP-3" does not correspond to a naturally secreted human hormone. Humans produce GLP-1 and GLP-2 from proglucagon processing, but no endogenous GLP-3 exists. Instead, the term has become informal shorthand for synthetic triple agonist peptides, most notably retatrutide (LY3437943), engineered to engage three receptors at once: the glucagon-like peptide-1 receptor (GLP-1R), the glucose-dependent insulinotropic polypeptide receptor (GIPR), and the glucagon receptor (GCGR).

Retatrutide is a 39-amino-acid acylated peptide built on a glucagon-based scaffold. Its C20 fatty diacid moiety promotes strong albumin binding, extending its pharmacokinetic half-life to approximately six days. In animal cell models, this structural feature alters receptor residence time and sustains signaling across pancreatic islets, hepatocytes, and central nervous system neurons. The coordinated activation of all three receptors drives glucose-dependent insulin secretion, appetite suppression via hypothalamic circuits, and increased energy expenditure, effects that no single-receptor agonist can fully replicate.

GLP-2-T, often associated with tirzepatide-class analogs (LY3298176), follows a related but distinct logic. These truncated peptide analogs are 39-amino-acid dual incretins with a C20 fatty diacid side chain, a molecular weight around 4.8 kDa, and an in-vivo half-life of roughly five days. Their "twincretin" behavior, balanced GIPR agonism paired with biased GLP-1R activation, targets pancreatic beta-cells, gut epithelium, and CNS appetite circuits in mammalian models.

Key distinction: GLP-3 engages three receptors simultaneously; GLP-2-T engages two. Both are tools for dissecting how multi-receptor incretin signaling reshapes metabolic cell networks.

Truncated GLP-2 variants, such as GLP-2(11-33) and the dipeptidyl peptidase IV (DPP-IV) metabolite GLP-2(3-33), serve as pharmacological probes in intestinal and endocrine cell research. DPP-IV cleaves both GLP-1 and GLP-2 at the N-terminus in vivo, generating metabolites with altered receptor binding and reduced signaling intensity. Studying these truncations helps researchers understand how peptide half-life and structural integrity govern GLP-2 receptor (GLP-2R) pharmacology in gut cells.

Growth Hormone Secretagogues and Their Cellular Mechanisms in Animal Models

Growth Hormone Secretagogues and Their Cellular Mechanisms in Animal Models

Growth hormone secretagogues (GHS) represent a structurally diverse class of peptides that share one defining feature: activation of the growth hormone secretagogue receptor 1a (GHSR1a), a 366-amino-acid, seven-transmembrane G-protein-coupled receptor (GPCR). GHSR1a was originally characterized as the receptor for synthetic GHS peptides before ghrelin was identified as its endogenous ligand.

GHSR1a is highly expressed in:

  • Anterior pituitary somatotrope cells (primary site of GH release)
  • Hypothalamic neurons (appetite and energy regulation)
  • Pancreatic tissue
  • Cardiac and neuronal cells (neuroprotection and cardiovascular signaling)
  • Thymic immune cells

One biologically unusual feature of GHSR1a is its high constitutive activity, it signals even without a ligand present. Two endogenous molecules modulate this baseline activity: octanoylated ghrelin, which acts as a full agonist, and LEAP2 (liver-expressed antimicrobial peptide 2), which functions as an inverse agonist and antagonist.

In 2026, the most studied synthetic GHS peptides include CJC-1295 (with or without drug affinity complex/DAC), ipamorelin, hexarelin, GHRP-2, GHRP-6, sermorelin, tesa, and the small-molecule MK-677 (ibutamoren). Researchers working with IPA peptides and related compounds apply these agents to pituitary and hypothalamic cell cultures to map intracellular signaling cascades, G-protein activation, calcium flux, and downstream transcriptional responses, that govern GH synthesis and secretion.

Beyond GH release, GHSR signaling exerts pleiotropic effects on cell populations across multiple tissues, including modulation of glucose and lipid metabolism, gastrointestinal motility, neuronal survival, and immune function.

Peptides in Basic Cell Biology Across Animal and Plant Systems

Peptides in Basic Cell Biology Across Animal and Plant Systems

A critical boundary in understanding peptides in basic cell biology, how GLP-3, GLP-2-T, and growth hormone secretagogues interact with animal and plant cells, is the receptor distribution question. The receptors central to GLP-3, GLP-2-T, and GHS pharmacology (GLP-1R, GIPR, GCGR, GLP-2R, and GHSR1a) are all vertebrate-specific GPCRs. Plant genomes do not encode these receptors. No credible evidence from current plant cell biology literature supports canonical GLP-3, GLP-2-T, or GHSR-mediated signaling in plant cells.

This distinction matters practically. Researchers designing study design peptides protocols for cross-kingdom comparative work must account for the absence of these receptor systems in plant models. Any peptide effects observed in plant cell assays would reflect non-specific or structural interactions rather than receptor-mediated signaling.

In contrast, animal cell models, particularly mammalian pancreatic islets, hepatocytes, pituitary cultures, and neuronal lines, remain the primary systems for applying these compounds. Researchers sourcing wholesale peptides for sale for preclinical programs consistently apply GLP-3 and GLP-2-T analogs in these controlled mammalian settings to interrogate incretin network biology.

All three peptide classes carry consistent "research use only" designations in 2026 catalogs. GLP-3/retatrutide remains in Phase 3 clinical trials and is not FDA-approved. GLP-2-T/tirzepatide-class research analogs are similarly restricted to laboratory use. These compounds are not intended for human or veterinary therapy outside approved clinical frameworks.

Research Context Note: The convergence of triple and dual incretin agonists as cell-biology tools marks a central 2026 development. Moving from single-receptor to multi-receptor agonists allows researchers to map how simultaneous receptor activation reshapes signaling networks in pancreatic beta-cells, hepatocytes, and CNS neurons, producing effects on glucose homeostasis and appetite that single-target compounds cannot replicate.

For researchers focused on tissue-level outcomes, tissue repair peptides and stimuli responsive peptides offer complementary frameworks for studying how peptide-receptor interactions translate into cellular repair and adaptive responses in animal models.

Conclusion

The study of peptides in basic cell biology, how GLP-3, GLP-2-T, and growth hormone secretagogues interact with animal and plant cells, reveals a field defined by precision engineering and receptor specificity. GLP-3/retatrutide-class triple agonists and GLP-2-T/tirzepatide-class dual incretins are powerful probes for dissecting multi-receptor metabolic signaling in mammalian cell systems. GHS peptides extend this toolkit into pituitary and hypothalamic biology through GHSR1a-mediated pathways.

Actionable next steps for researchers:

  1. Confirm receptor expression profiles in your specific cell line before selecting a GLP-class or GHS peptide, receptor absence invalidates the model.
  2. Account for DPP-IV-mediated truncation when designing in-vitro assays with GLP-1 or GLP-2 analogs; use DPP-IV-resistant variants or inhibitors where appropriate.
  3. Apply plant cell models only for non-receptor-mediated peptide studies; do not extrapolate GLP-3 or GHSR findings to plant systems.
  4. Source research-grade compounds with certificates of analysis and maintain strict research-use-only protocols in compliance with institutional guidelines.
  5. Monitor Phase 3 trial data for retatrutide, the mechanistic insights from clinical outcomes will refine in-vitro model design.
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptides-in-basic-cell-biology-how-glp-3-glp-2-t-and-growth-hormone-secretagogue.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-03 13:06:212026-09-03 13:06:21Peptides in Basic Cell Biology: How GLP-3, GLP-2-T, and Growth Hormone Secretagogues Interact With Animal and Plant Cells
Complete Guide to Research Peptides: Types, Mechanisms, and Laboratory Use Cases

Complete Guide to Research Peptides: Types, Mechanisms, and Laboratory Use Cases

August 14, 2026/0 Comments/in Uncategorized/by

Over 7,000 naturally occurring peptides have been identified in the human body, yet the global research peptide market continues to expand as scientists uncover new ways these short amino acid chains regulate nearly every biological system. This complete guide to research peptides: types, mechanisms, and laboratory use cases is designed to serve as a foundational reference for researchers, students, and science professionals who need a clear, organized overview of how peptides are classified, how they work, and where they are being studied today.

Key Takeaways

  • Research peptides are short chains of 2 to 50 amino acids studied primarily in preclinical settings, with many lacking formal human approval.
  • Peptides are classified by their mechanism of action, including receptor agonism, membrane targeting, and enzyme modulation.
  • Major research categories include GLP-1 agonists, growth hormone secretagogues, regenerative peptides, neuropeptides, and longevity compounds.
  • Laboratory use cases span tissue repair, metabolic biology, angiogenesis, and mitochondrial function.
  • Formulation and stability challenges remain key areas of active investigation in peptide science.

What Are Research Peptides and How Are They Defined

Research peptides are amino acid chains typically ranging from 2 to 50 residues in length. This size range places them between small-molecule drugs and full-size proteins, giving them a distinct pharmacological profile. Most are studied in preclinical or early-phase settings, and many that appear in research catalogs have not received regulatory approval for human use.

What Are Research Peptides and How Are They Defined

Their appeal in laboratory research comes from several properties. Peptides can be synthesized with high precision, modified to improve stability, and designed to interact with specific receptors or cellular pathways. Unlike many small-molecule drugs, they often mimic endogenous signaling molecules, which makes them valuable tools for studying how biological systems respond to targeted stimulation or inhibition. For a deeper look at how these compounds compare with conventional pharmaceuticals, see Peptides vs Classic Small-Molecule Drugs.

Key structural features of research peptides:

Feature Description
Chain length 2 to 50 amino acids
Molecular weight Typically 500 to 5,000 Da
Synthesis method Solid-phase peptide synthesis (SPPS)
Stability Often sensitive to heat, light, and proteases
Selectivity High receptor or pathway specificity

Major Types and Mechanistic Families in the Complete Guide to Research Peptides

Understanding peptide types requires looking at both structure and function. The most useful classification system in research settings groups peptides by their primary mechanism of action.

GLP-1 Agonists and Metabolic Peptides

GLP-1 receptor agonists are among the most clinically advanced peptide classes. They bind to glucagon-like peptide receptors to regulate insulin secretion, appetite, and energy metabolism. Newer multi-agonist designs, including triple-agonist compounds, are expanding the research scope considerably. The GLP-3 Retatrutide and triple-agonist peptides research overview covers how these next-generation compounds are reshaping metabolic science.

Growth Hormone Secretagogues

These peptides stimulate the pituitary gland to release growth hormone. Common examples include ipamorelin, sermorelin, and CJC-1295. They work primarily through ghrelin receptors or growth hormone-releasing hormone receptors. The CJC-1295 mechanism and pharmacokinetic comparison is a useful resource for understanding how DAC modification changes half-life and receptor interaction.

Regenerative and Tissue Repair Peptides

BPC-157 and TB-500 are the most widely studied compounds in this category. Research suggests they may influence angiogenesis, collagen synthesis, and cellular migration. The BPC-157 vs TB-500 complete research comparison provides a detailed side-by-side analysis of their proposed mechanisms and laboratory applications.

Neuropeptides and Cognitive Research Compounds

Selank, Semax, and BDNF-related peptides are studied for their roles in neuroplasticity, anxiety modulation, and cognitive function. These compounds interact with receptors in the central nervous system and are often administered intranasally in research settings. See the Selank peptide research benefits and mechanism of action for a detailed breakdown.

Longevity and Mitochondrial Peptides

MOTS-c, SS-31, and Epithalon represent a growing class of compounds studied for their effects on cellular aging, mitochondrial efficiency, and senescence pathways. The MOTS-c mitochondrial research themes page covers the current state of this research area.

Laboratory Use Cases Covered in This Complete Guide to Research Peptides

Laboratory Use Cases Covered in This Complete Guide to Research Peptides

The practical applications of research peptides span multiple biological domains. Below are the primary laboratory use cases documented in current preclinical literature.

Tissue Repair and Regenerative Biology
Peptides such as BPC-157 are studied in wound healing models, tendon repair assays, and gut mucosal regeneration. Their proposed effects on nitric oxide pathways and growth factor upregulation make them valuable tools in regenerative biology research.

Metabolic and Endocrine Research
GLP-1 agonists and growth hormone secretagogues are used in metabolic studies examining insulin sensitivity, adipose tissue dynamics, and hormonal feedback loops. The complete guide to peptide mechanisms covering GLP-1 and growth hormone peptides explains the molecular detail behind these pathways.

Neuroprotection and Brain Research
Neuropeptides are used in models of neuroinflammation, cognitive decline, and stress response. Researchers study how these compounds modulate BDNF expression, serotonin signaling, and HPA axis activity.

Skin, Hair, and Connective Tissue Research
GHK-Cu and related copper-binding peptides are studied for their effects on collagen gene expression, antioxidant activity, and dermal repair. The GHK-Cu peptide and collagen research overview covers the current evidence base.

Mitochondrial and Aging Biology
SS-31 and MOTS-c are used in studies examining mitochondrial membrane potential, ROS production, and age-related cellular decline. These compounds are at the frontier of longevity research.

Formulation, Storage, and Administration Challenges

Formulation, Storage, and Administration Challenges

Peptides present unique challenges in research settings that differ significantly from small-molecule compounds.

  • Proteolytic degradation: Peptides are broken down rapidly by enzymes in biological fluids, requiring modified analogs or protective formulations.
  • Reconstitution accuracy: Lyophilized peptides must be reconstituted carefully to ensure dosing precision. Tools like peptide calculators help researchers maintain accuracy.
  • Storage requirements: Most research peptides require storage at -20°C or lower to maintain stability.
  • Routes of administration: Subcutaneous injection is most common in research models, though intranasal and oral routes are being studied for specific compounds.

"Stability and purity are the two most critical variables in peptide research. A compound that degrades before reaching its target cannot produce reliable data."

These formulation considerations are especially relevant when working with multi-peptide stacks or novel delivery systems currently under investigation.

Conclusion

This complete guide to research peptides: types, mechanisms, and laboratory use cases provides a working framework for understanding one of the most dynamic areas in modern biochemistry. As of 2026, hundreds of peptide compounds are under active preclinical and clinical evaluation, spanning metabolic disease, neurological research, regenerative medicine, and aging biology.

Actionable next steps for researchers:

  1. Identify the mechanistic family most relevant to your research question before selecting a compound.
  2. Review published preclinical data for your target peptide, paying close attention to model species and dosing protocols.
  3. Confirm purity and third-party testing documentation before using any research peptide in a laboratory setting.
  4. Consult regulatory guidance in your jurisdiction, as the legal status of research peptides varies by country and application.
  5. Use the internal resources linked throughout this guide to explore specific peptide categories in greater depth.

Peptide science is advancing rapidly. Staying current with mechanistic research and emerging compound classes is essential for anyone working at the intersection of biochemistry, pharmacology, and translational medicine.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/complete-guide-to-research-peptides-types-mechanisms-and-laboratory-use-cases.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-14 13:06:382026-08-14 13:06:38Complete Guide to Research Peptides: Types, Mechanisms, and Laboratory Use Cases
How Researchers Use Tesamorelin and Ipamorelin Together vs Separately

How Researchers Use Tesamorelin and Ipamorelin Together vs Separately

August 13, 2026/0 Comments/in Uncategorized/by

Only one peptide in the growth hormone secretagogue class has ever received FDA approval: tesa, cleared specifically for HIV-associated lipodystrophy. Every other compound in this space, including ipamorelin, remains strictly in the research domain. That regulatory gap matters enormously when examining how researchers use tesa and ipamorelin together vs separately, because it shapes which questions are scientifically answerable today and which remain speculative.

This guide focuses on research design logic, not dosing protocols. The goal is to help investigators and informed readers understand the mechanistic rationale behind each compound used alone, and the theoretical (but largely unvalidated) basis for studying them as a stack.

Key Takeaways

  • Tesamorelin is a GHRH analog with an established clinical evidence base; ipamorelin is a ghrelin mimetic with a distinct receptor target and no approved indication.
  • Used separately, each compound acts through a different node of the GH axis, making their individual pharmacology well-characterized in isolation.
  • No peer-reviewed clinical trials have validated the tesa-ipamorelin combination as of 2026; reported trial programs remain in early or unconfirmed stages.
  • Researchers examining the stack must extrapolate safety considerations from GH-class risk data rather than combination-specific studies.
  • Monotherapy remains the methodological standard; combination use is niche, experimental, and requires careful study design justification.

Tesamorelin and Ipamorelin: Two Different Mechanisms on the Same Axis

Understanding how researchers use tesa and ipamorelin together vs separately begins with recognizing that these two peptides do not duplicate each other, they target different receptors within the same growth hormone axis.

Tesamorelin is a synthetic analog of growth hormone-releasing hormone (GHRH). It binds to GHRH receptors on the anterior pituitary, stimulating pulsatile GH secretion. Its approved clinical use centers on reducing visceral adipose tissue in HIV-positive adults with lipodystrophy, and its metabolic and IGF-1 effects are well-documented in that population. For a deeper look at the science behind this compound, see this overview of what tesa is and the science behind it.

Ipamorelin, by contrast, is a selective growth hormone secretagogue receptor agonist (GHS-R1a), a ghrelin mimetic. It triggers GH release through a separate receptor pathway and is noted in preclinical literature for producing relatively selective GH pulses with minimal impact on cortisol or prolactin compared to earlier secretagogues.

Tesamorelin and Ipamorelin: Two Different Mechanisms on the Same Axis

The table below summarizes the key mechanistic distinctions:

Feature Tesamorelin Ipamorelin
Receptor target GHRH receptor GHS-R1a (ghrelin receptor)
Mechanism class GHRH analog Ghrelin mimetic
Regulatory status FDA-approved (limited indication) Research use only
Primary studied effect Visceral fat reduction, IGF-1 elevation Selective GH pulse stimulation
Cortisol/prolactin impact Minimal in approved studies Low relative to older GHS compounds

Because the two compounds act at distinct receptor sites, researchers theorize that co-administration could produce additive or synergistic GH stimulation, engaging both the GHRH and ghrelin pathways simultaneously. This is the core rationale behind studying them as a stack.

How Researchers Use Tesamorelin and Ipamorelin Together vs Separately in Study Design

When designing a GH-axis study, the first methodological question is whether the research question requires isolating a single mechanism or probing pathway interactions. This is where the choice between monotherapy and combination protocols becomes a scientific decision, not a preference.

Monotherapy Research: The Established Standard

Tesamorelin monotherapy has the strongest evidentiary foundation. Studies in HIV-associated lipodystrophy populations have documented reductions in hepatic fat, improvements in triglyceride profiles, and measurable IGF-1 changes. Researchers working in metabolic health contexts often use tesa as a comparator anchor precisely because its effects are quantifiable against a known baseline.

Ipamorelin monotherapy, while lacking approved-indication data, has been studied in preclinical and early-phase models for its GH pulse characteristics. Its selectivity profile makes it a useful research tool when investigators want to stimulate GH release without the confounding hormonal noise associated with less selective secretagogues.

"Monotherapy designs allow researchers to attribute observed outcomes to a single compound's mechanism, a methodological clarity that combination protocols inherently sacrifice."

Researchers interested in the broader context of how these compounds fit within metabolic peptide research may find value in reviewing the top research peptides for metabolic health and how tesa compares to other secretagogues in the tesa vs sermorelin analysis.

Combination Research: Theoretical Synergy Without Peer-Reviewed Validation

As of 2026, no peer-reviewed clinical trials have been published validating the tesa-ipamorelin combination. Vendor protocol guides and community forums describe a theoretical synergy based on dual-node GH axis stimulation, but this framing represents hypothesis generation, not established pharmacology.

A reported clinical trial program, sometimes referenced under the informal designation SYNERGY-1, -2, and -3, has been cited in research community discussions, but peer-reviewed results from these programs are not yet available. Researchers should treat any combination protocol claims with the same scrutiny applied to any unvalidated intervention.

Combination Research: Theoretical Synergy Without Peer-Reviewed Validation

For researchers considering multi-peptide formulations, pre-blended formats exist that combine tesa with other GH-axis compounds. The Tesamorelin CJC-1295 Ipamorelin 12mg blend and related reconstitution protocols illustrate how vendors have operationalized combination formats, though these are distinct from peer-reviewed study designs.

Safety Considerations and Research Limitations

When researchers use tesa and ipamorelin together vs separately, safety analysis must account for the absence of combination-specific clinical data.

Extrapolating From GH-Class Risk Profiles

For tesa alone, documented considerations include effects on glucose metabolism, potential IGF-1 elevation beyond target ranges, and liver-related monitoring in metabolic populations. A detailed review of tesa side effects provides a structured reference for these considerations.

For combination use, researchers must extrapolate from:

  • GH-class adverse event profiles observed across secretagogue research broadly
  • Additive IGF-1 effects, which may exceed what either compound produces alone
  • Glucose homeostasis disruption, a known class-level concern with sustained GH elevation
  • Limited safety reporting, since no large-scale combination trial data exists

Designing Responsible Combination Studies

Researchers approaching combination protocols should consider the following framework:

  1. Establish individual compound baselines before introducing the stack
  2. Define clear IGF-1 and glucose monitoring endpoints
  3. Document receptor pathway rationale explicitly in study design
  4. Acknowledge the absence of peer-reviewed combination pharmacokinetic data
  5. Distinguish between vendor-described protocols and validated research methodology

Accurate dosing precision is also critical in any multi-compound design. Tools discussed in resources on peptide calculators for tesa and ipamorelin can support reconstitution accuracy, though they do not substitute for validated protocols.

Designing Responsible Combination Studies

Conclusion

The question of how researchers use tesa and ipamorelin together vs separately is ultimately a question about matching study design to the state of available evidence. Tesamorelin monotherapy stands on a foundation of clinical trial data and regulatory approval within a defined indication. Ipamorelin monotherapy offers a mechanistically distinct tool for GH pulse research with a selective profile. The combination, while theoretically grounded in dual-node GH axis stimulation, lacks peer-reviewed validation as of 2026.

Actionable next steps for researchers:

  • Default to monotherapy designs when the research question can be answered with a single compound
  • If combination protocols are pursued, pre-specify the mechanistic rationale and safety monitoring plan in study documentation
  • Distinguish vendor marketing claims from published pharmacology when evaluating the stack
  • Monitor for peer-reviewed outputs from any registered combination trial programs before incorporating combination data into literature reviews
  • Use validated reconstitution and dosing tools to maintain experimental precision regardless of protocol type

The science of GH-axis peptide research is advancing, but rigorous methodology requires acknowledging what the evidence currently supports, and what it does not.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/how-researchers-use-tesa-and-ipamorelin-together-vs-separately.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-13 13:05:022026-08-13 13:05:02How Researchers Use Tesamorelin and Ipamorelin Together vs Separately
Page 1 of 212
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top