Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: intranasal peptide research

Glow Blend vs Klow Blend: How to Compare Injectable-Style and Intranasal Research Formulations by Endpoint

Glow Blend vs Klow Blend: How to Compare Injectable-Style and Intranasal Research Formulations by Endpoint

November 1, 2026/0 Comments/in Uncategorized/by

Multi-peptide blends are not additive by default. Two formulations can share several components yet produce measurably different outcomes simply because their ratios, total mass, and intended delivery routes diverge. Understanding Glow Blend vs Klow Blend: How to Compare Injectable-Style and Intranasal Research Formulations by Endpoint requires moving beyond a simple ingredient checklist and into a rigorous, endpoint-first framework.

Key Takeaways

  • Glow Blend and Klow Blend differ in peptide ratios and total mass, which directly changes which assays are most appropriate.
  • Route of administration, injectable-style vial versus potential intranasal use, affects bioavailability and, therefore, endpoint interpretation.
  • Neither blend should be assumed to behave as the sum of its parts; synergistic and antagonistic interactions must be tested, not inferred.
  • Endpoint selection should drive formulation choice, not the other way around.
  • Documentation updates released in late 2026 clarify reconstitution and dosing parameters for both blends, making protocol alignment easier.

Compositional Differences That Drive Endpoint Selection
Compositional Differences That Drive Endpoint Selection

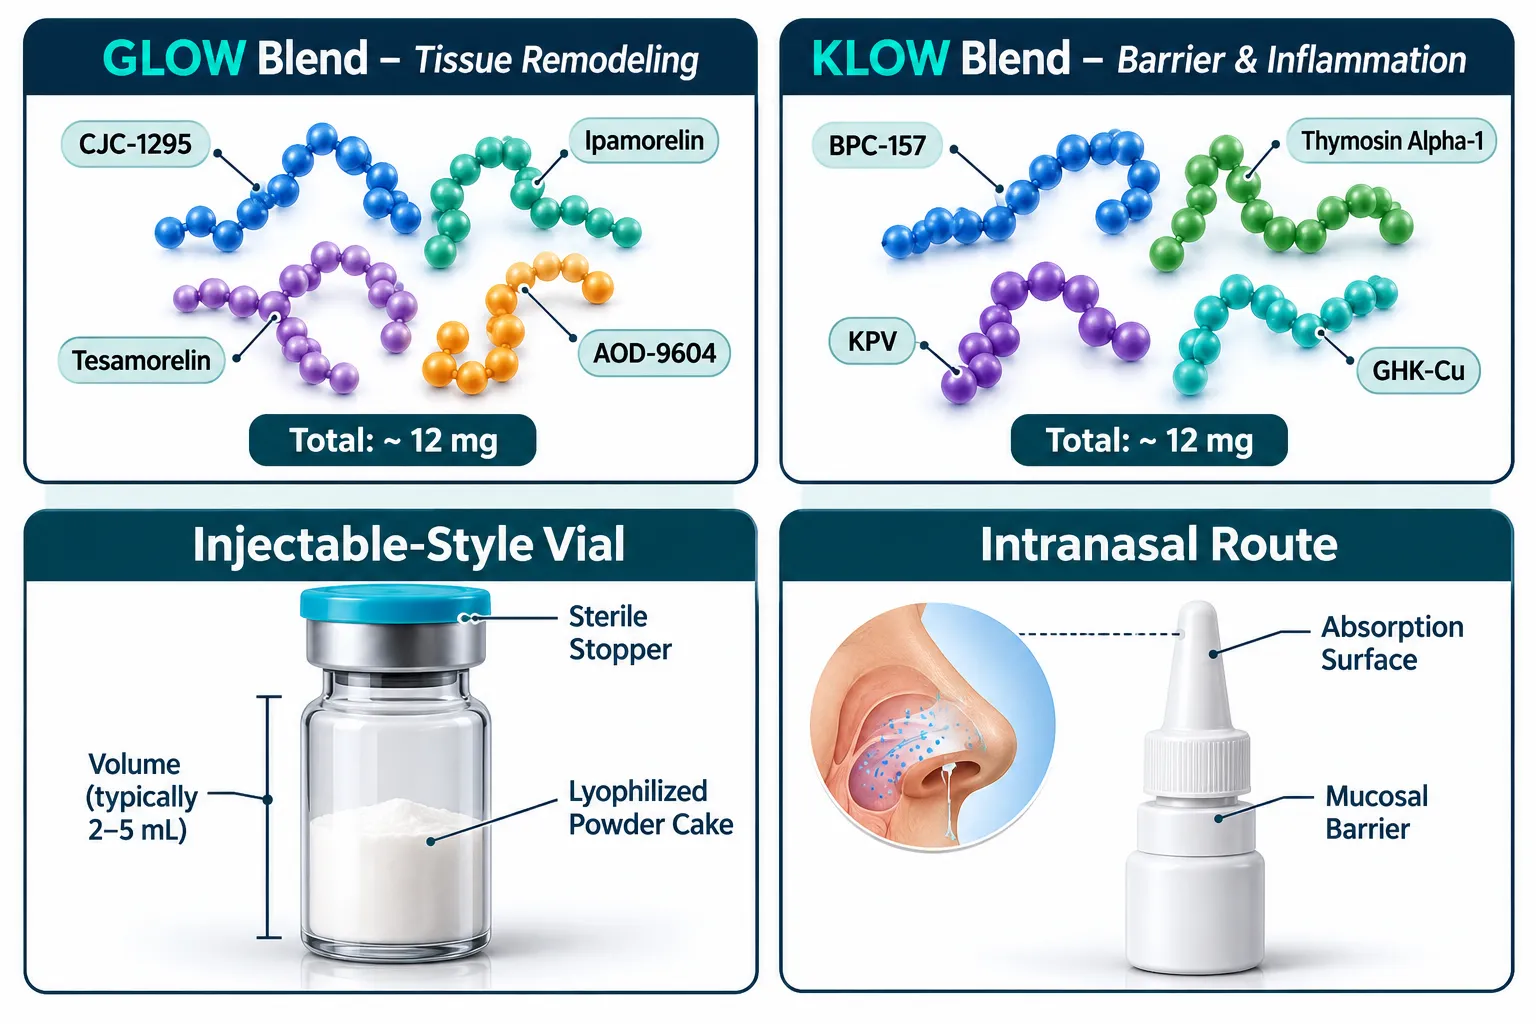
Glow Blend is a higher-mass formulation oriented toward tissue remodeling endpoints. It typically combines Tesamorelin, CJC-1295, Ipamorelin, and AOD-9604 in a configuration that emphasizes growth hormone secretagogue activity alongside lipolytic signaling. Researchers interested in collagen turnover, extracellular matrix remodeling, or adipose tissue dynamics have a clearer mechanistic rationale for selecting Glow Blend as their primary vehicle.

Klow Blend, by contrast, is engineered around inflammation modulation and gut barrier integrity. Its peptide profile shifts the ratio toward compounds with documented anti-inflammatory and epithelial-support profiles. The total mass per vial is lower than Glow Blend, which matters when designing dose-response curves, a lower ceiling concentration changes the shape of a sigmoidal curve and can obscure effects that would otherwise reach statistical significance.

A blend's label tells you what is inside. The ratio tells you what it will do.

For researchers working with Tesamorelin AOD9604 CJC1295 Ipamorelin 12mg blend dosage protocols, understanding how mass and ratio interact is foundational before any endpoint assay is run.

Key compositional contrasts at a glance:

Feature Glow Blend Klow Blend
Primary mechanistic target Tissue remodeling / GH axis Inflammation / gut barrier
Total peptide mass Higher Lower
AOD-9604 presence Yes Formulation-dependent
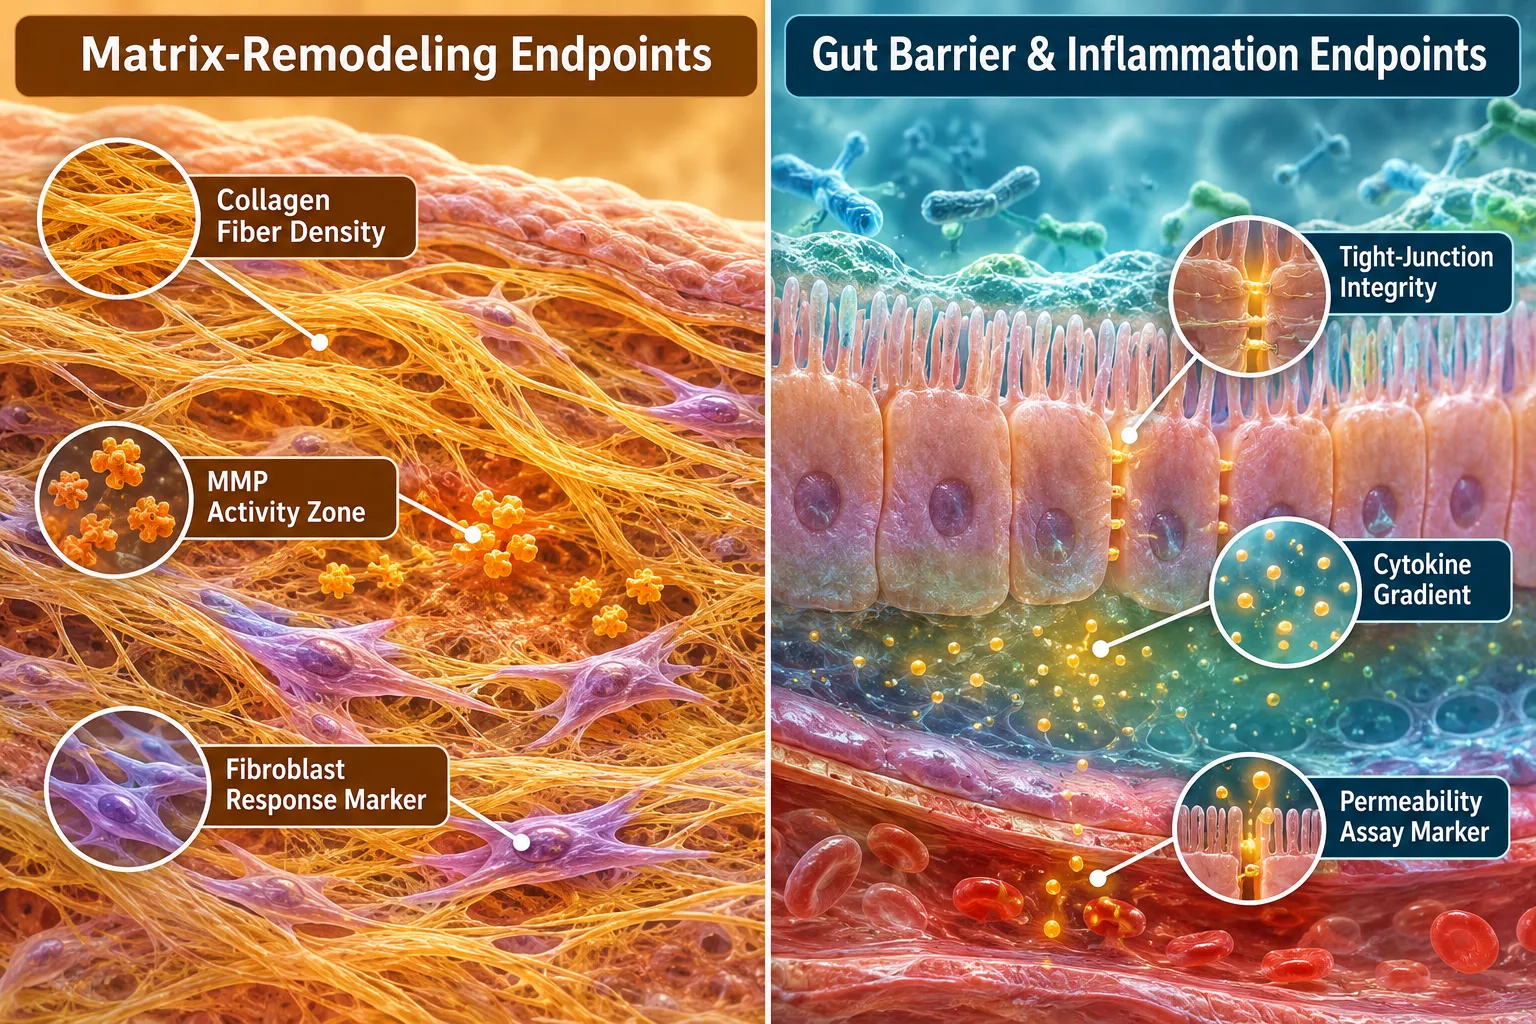
Recommended primary assay MMP activity, collagen markers Cytokine panels, TEER assay

Route-Dependent Exposure: Injectable-Style Vials vs Intranasal Use

Both Glow Blend and Klow Blend are supplied as lyophilized powder in injectable-style vials. This format is standard for multi-peptide research preparations because lyophilization preserves stability across the peptide stack. Reconstitution protocols for the Tesamorelin CJC1295 Ipamorelin 12mg blend provide a practical reference point for handling these vials correctly before any endpoint study begins.

Intranasal delivery of either blend remains unofficial and undocumented as of late 2026. Several research groups have explored nasal mucosal absorption as an alternative route for single-peptide compounds, Semax nasal spray formulations represent a well-documented example, but extending that logic to a complex multi-peptide blend introduces significant variables.

Specifically, intranasal delivery changes:

  • First-pass metabolism bypass, nasal mucosa avoids hepatic first pass, but enzymatic degradation at the mucosal surface is not uniform across all peptides in a blend.
  • Relative bioavailability per component, larger peptides such as Tesamorelin absorb less efficiently than smaller fragments, meaning the effective ratio inside the blend shifts after administration.
  • Endpoint interpretation, if the absorbed ratio differs from the formulated ratio, any assay result tied to a specific mechanism becomes difficult to attribute cleanly.

For endpoint studies demanding reproducibility, the injectable-style route provides a more controlled exposure profile. Researchers considering nasal delivery for either blend should treat it as a separate experimental variable, not a substitute administration method.


Comparing Glow Blend vs Klow Blend by Specific Research Endpoints
Comparing Glow Blend vs Klow Blend by Specific Research Endpoints

The most defensible way to approach Glow Blend vs Klow Blend: How to Compare Injectable-Style and Intranasal Research Formulations by Endpoint is to define the endpoint first, then evaluate which formulation's mechanistic profile aligns with that outcome measure.

Matrix-Remodeling Assays

For endpoints such as MMP-2/MMP-9 activity, hydroxyproline content, or fibroblast proliferation rate, Glow Blend's higher GH-secretagogue load creates a relevant signaling environment. Dose-response studies using Tesamorelin CJC1295 Ipamorelin blend dose protocols show that GH pulse amplitude correlates with downstream matrix changes in ex vivo models.

Barrier Integrity and Cytokine Endpoints

Klow Blend is more appropriate when the endpoint involves transepithelial electrical resistance (TEER), tight-junction protein expression (ZO-1, occludin), or multi-cytokine inflammatory profiling. The IPA Sermorelin stack research literature further supports the idea that ipamorelin-containing stacks with modified ratios can suppress pro-inflammatory signaling in gut epithelial models.

Oxidative Stress Endpoints

Some researchers have begun pairing either blend with mitochondrial-targeted peptides to extend endpoint panels. SS-31 mitochondrial research protocols offer a complementary framework when oxidative phosphorylation efficiency or ROS generation is a secondary endpoint.


Documentation, Regulatory Context, and Protocol Design in 2026
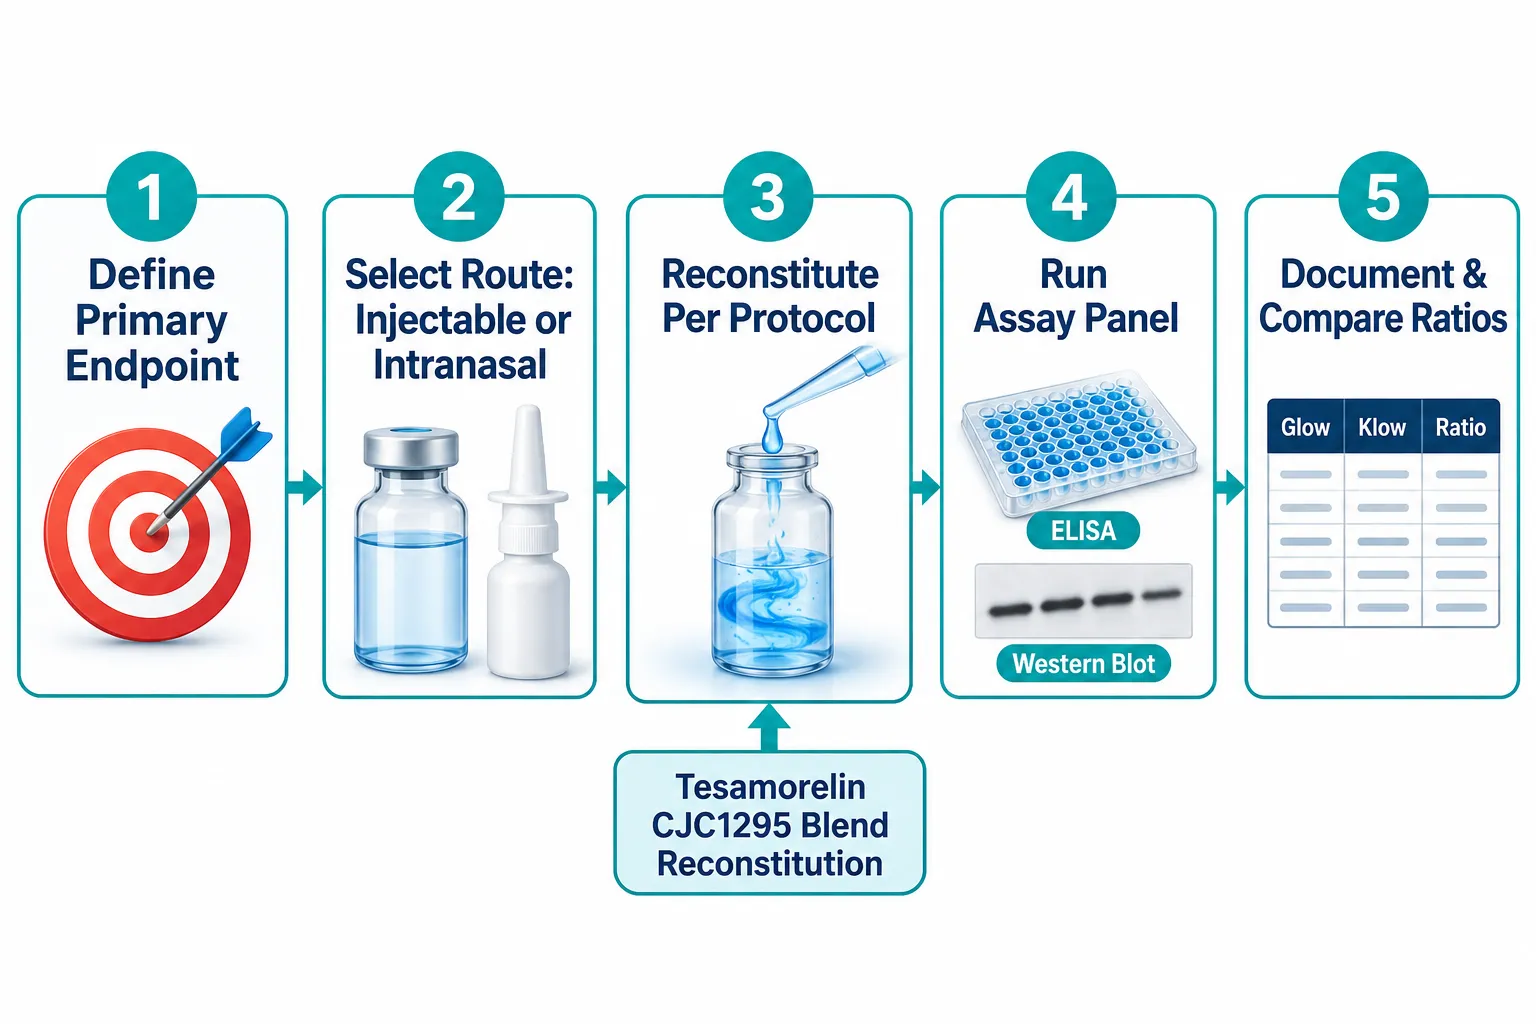
Documentation, Regulatory Context, and Protocol Design in 2026

Documentation updates released in October and November 2026 have clarified two critical points for researchers comparing these formulations:

  1. Reconstitution volume affects concentration nonlinearly when total peptide mass differs between blends. Standardizing vehicle volume without adjusting for mass will produce non-equivalent molar concentrations.
  2. Endpoint labeling in study records must specify which blend, which lot, and which route was used. Regulatory guidance increasingly treats multi-peptide blends as distinct research materials, not interchangeable variants.

Both blends are research-only materials. Neither has received regulatory approval for clinical use, and all comparative endpoint work must be conducted within an appropriate institutional research framework. Researchers should also note that comparing Glow Blend vs Klow Blend across endpoints is only valid when blinded controls, vehicle-only arms, and single-compound reference arms are included, otherwise, it is impossible to determine whether a significant result reflects the blend's combined action or a dominant single component.


Conclusion

Selecting between Glow Blend and Klow Blend is fundamentally an endpoint decision. Researchers focused on tissue remodeling, GH-axis dynamics, and extracellular matrix markers have stronger mechanistic alignment with Glow Blend. Those designing gut barrier, inflammatory, or epithelial permeability studies will find Klow Blend's profile more relevant.

Actionable next steps:

  • Define your primary endpoint before ordering either formulation.
  • Review the 2026 documentation updates for reconstitution and concentration calculations.
  • Include single-compound reference arms in every comparative study to avoid attribution errors.
  • Treat intranasal delivery as an independent experimental variable, not a default alternative route.
  • Cross-reference your assay panel against the blend's known mechanistic targets to ensure the endpoint you are measuring can actually be driven by the compounds present.

Rigor in formulation comparison begins with the question, not the blend.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/glow-blend-vs-klow-blend-how-to-compare-injectable-style-and-intranasal-research.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-01 14:03:302026-11-01 14:03:30Glow Blend vs Klow Blend: How to Compare Injectable-Style and Intranasal Research Formulations by Endpoint
Semax Nasal Spray in 2026: How to Grade Intranasal Evidence When Pharmacokinetic Data Are Missing

Semax Nasal Spray in 2026: How to Grade Intranasal Evidence When Pharmacokinetic Data Are Missing

October 15, 2026/0 Comments/in Uncategorized/by

Fewer than a dozen randomized controlled trials have ever examined Semax by any route of administration, yet the compound remains one of the most discussed research peptides in nootropic and stroke-recovery communities worldwide. That gap between clinical curiosity and clinical evidence is exactly why grading the available data demands a structured, methodologically honest approach.

This article addresses the core challenge of Semax nasal spray in 2026: how to evaluate intranasal research findings when human pharmacokinetic (PK) data are absent, incomplete, or derived entirely from animal models.

Key Takeaways

  • Semax nasal spray carries no FDA approval in 2026, and the agency has issued a negative effectiveness assessment for the compound.
  • The existing evidence base consists primarily of small, Russian, often unblinded intranasal trials with limited independent replication.
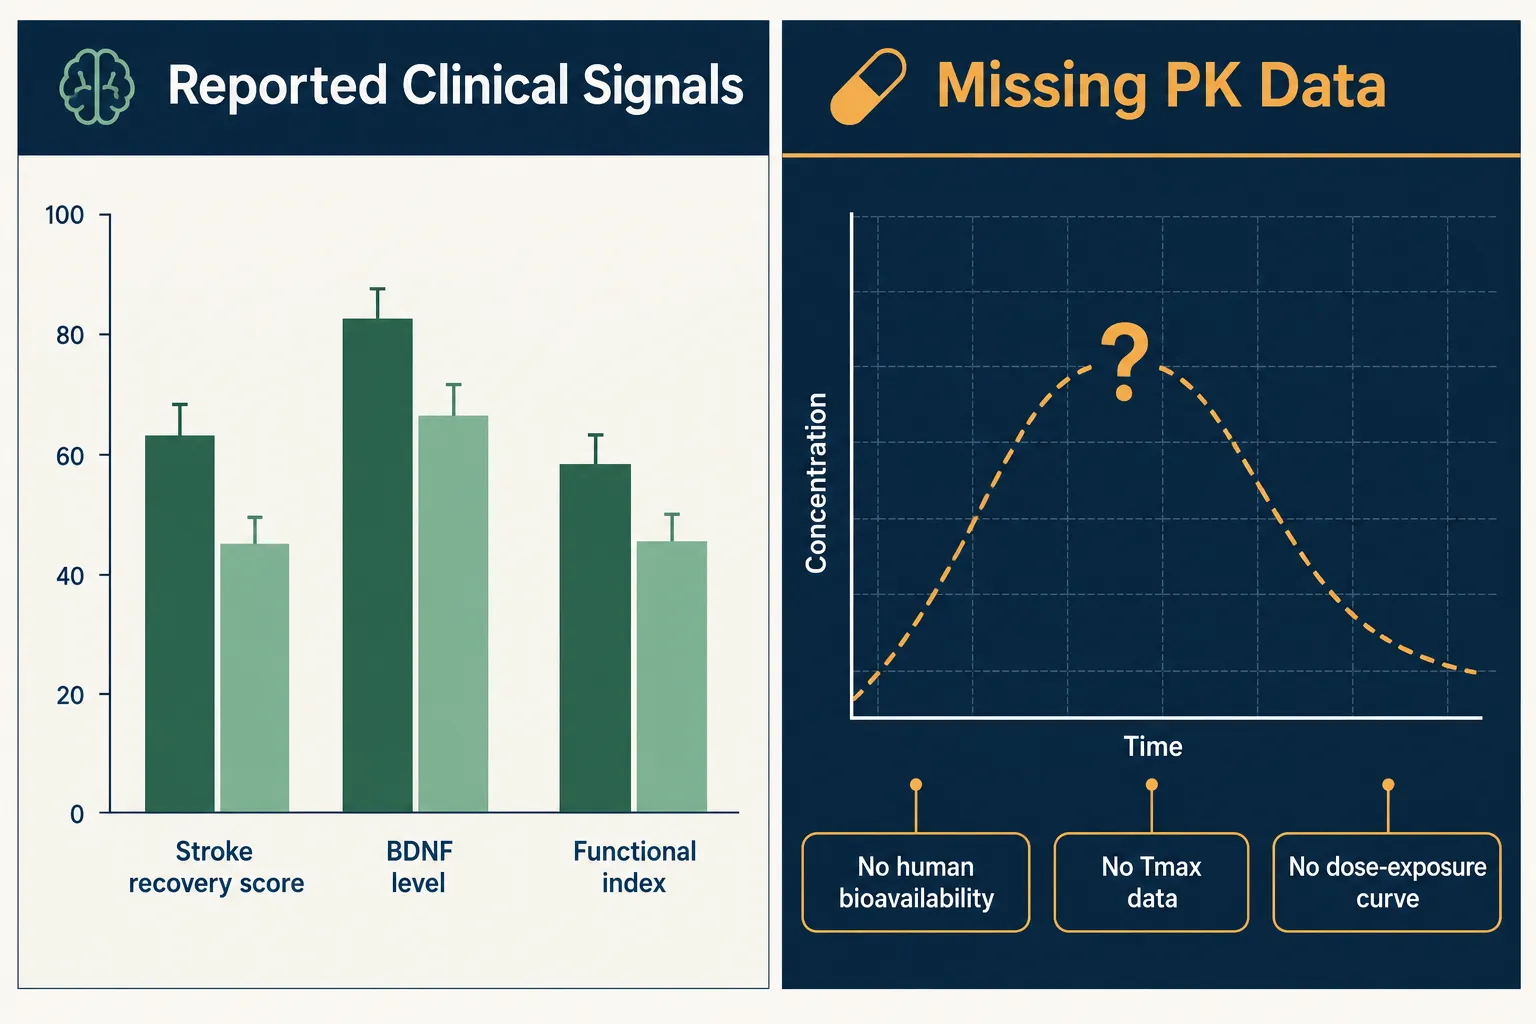
  • Human PK data, bioavailability, Cmax, Tmax, dose-exposure curves, are essentially absent for the intranasal route.
  • Animal models suggest rapid brain entry and equally rapid systemic degradation, but these findings cannot be directly extrapolated to human dosing.
  • Reviewers are increasingly applying route-specific grading criteria that treat missing PK data as a formal evidence gap, not a minor limitation.

Why the Pharmacokinetic Gap Matters for Intranasal Semax Research

Why the Pharmacokinetic Gap Matters for Intranasal Semax Research

When a compound is administered intranasally, its clinical effects depend entirely on how much of it actually reaches the target tissue and when. Without knowing the bioavailability fraction, the peak plasma or cerebrospinal concentration, or the time-to-peak for the intranasal route in humans, it becomes impossible to confirm that a reported effect was caused by the dose given, or by any dose at all.

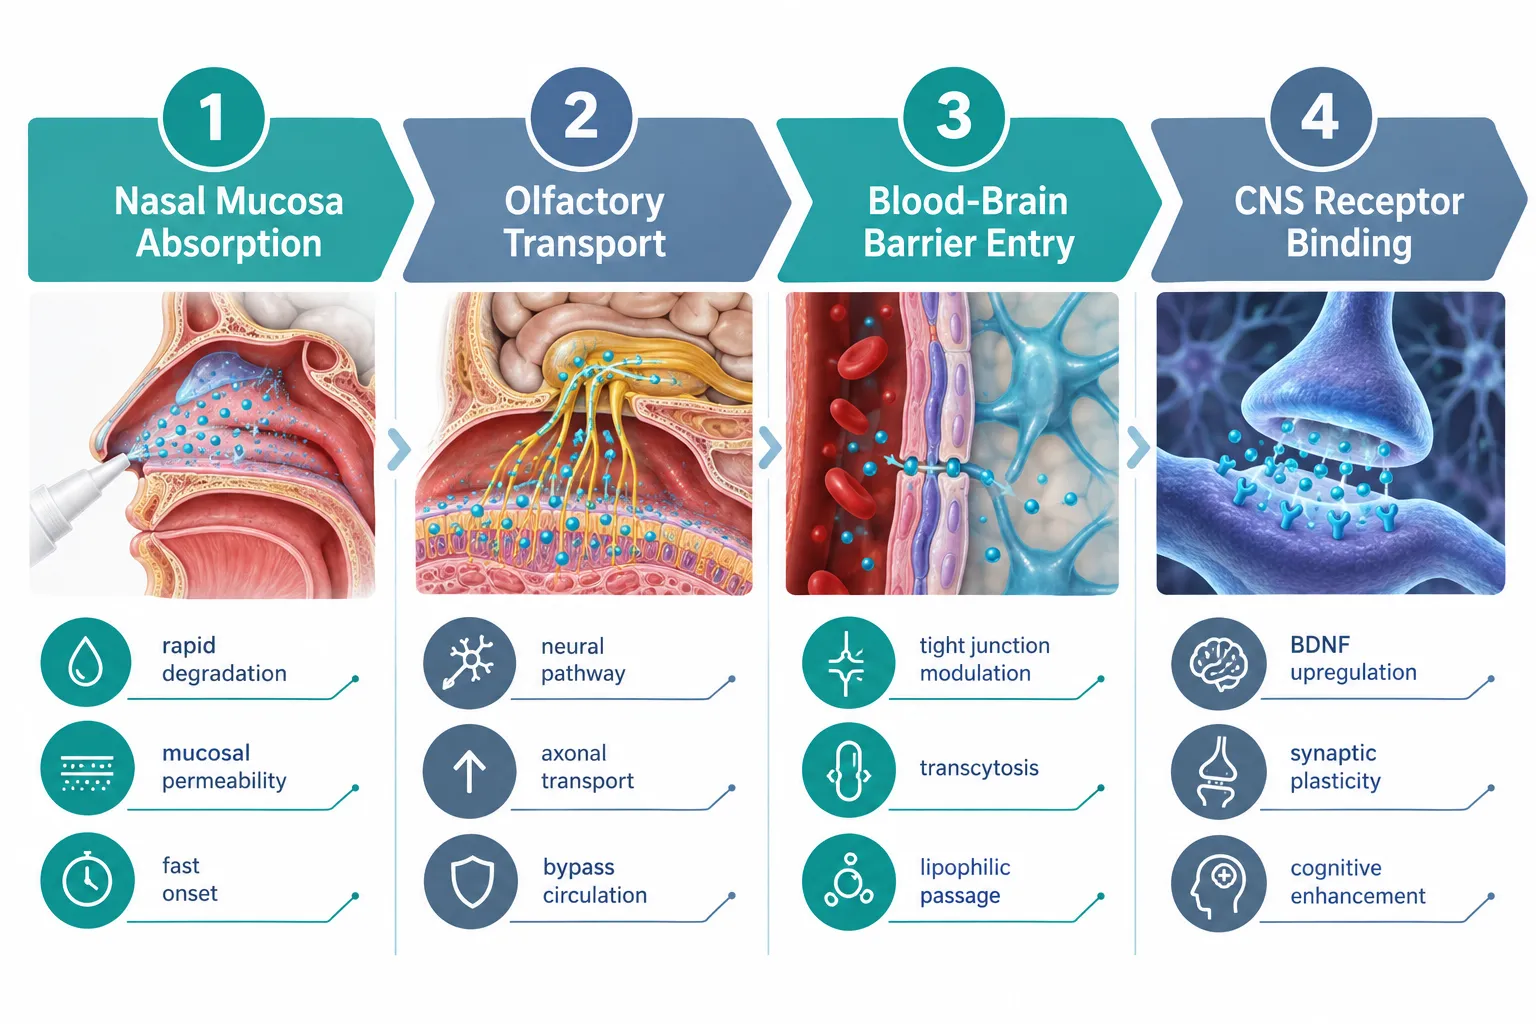
For Semax peptide, this is not a minor footnote. The compound is a synthetic heptapeptide derived from ACTH(4-7). Animal studies consistently show rapid olfactory-nerve transport into the brain following intranasal delivery, along with fast enzymatic degradation in systemic circulation. Those findings are promising, but they are not human PK data.

What animal models tell us:

  • Rapid mucosal absorption via olfactory epithelium
  • Short half-life in peripheral blood due to peptidase activity
  • Detectable CNS effects at low doses in rodent models

What they cannot confirm:

  • Human mucosal permeability and inter-individual variability
  • Actual brain concentrations achieved at clinical doses
  • Whether the dose-response curve in humans is linear or threshold-dependent

Without this information, any clinical signal observed in a trial is essentially floating, it cannot be anchored to a confirmed exposure level.


The Current Evidence Landscape for Semax Nasal Spray in 2026

The Current Evidence Landscape for Semax Nasal Spray in 2026

The regulatory picture is unambiguous. As of 2026, Semax nasal spray holds no approval from the FDA, and the agency's effectiveness assessment for the compound is negative. The existing clinical literature originates almost entirely from Russian research institutions, conducted primarily between the 1990s and 2010s.

"The absence of independent replication across different regulatory environments is itself a grading criterion, not just a contextual footnote."

Key characteristics of the existing trial base include:

Feature Typical Finding
Sample size Fewer than 100 participants per trial
Blinding Largely unblinded or single-blind
Control arm Variable; some trials lack placebo
Endpoint type Functional scores, neurological scales
Geographic diversity Predominantly single-country
Independent replication Minimal outside Russia

Clinical signals that do appear in the literature include improvements in stroke recovery scores, increases in BDNF-related markers, and modest gains on functional neurological assessments. These signals are not fabricated, they are simply unanchored to confirmed human exposure data, which limits their interpretive weight.

Use patterns in 2026 span two distinct populations: short-course clinical protocols in research settings, and long-term self-experimentation by nootropic users who are often combining Semax nasal spray with compounds such as Selank nasal spray or IPA nasal spray. The latter group operates entirely outside any monitored research framework.


A Structured Framework for Grading Intranasal Evidence When PK Data Are Missing

A Structured Framework for Grading Intranasal Evidence When PK Data Are Missing

Methodologists reviewing intranasal peptide research in 2026 are increasingly applying a route-specific grading overlay on top of standard tools like GRADE. The core principle: missing PK data must be coded as a formal evidence gap, not absorbed into the general "limitations" section.

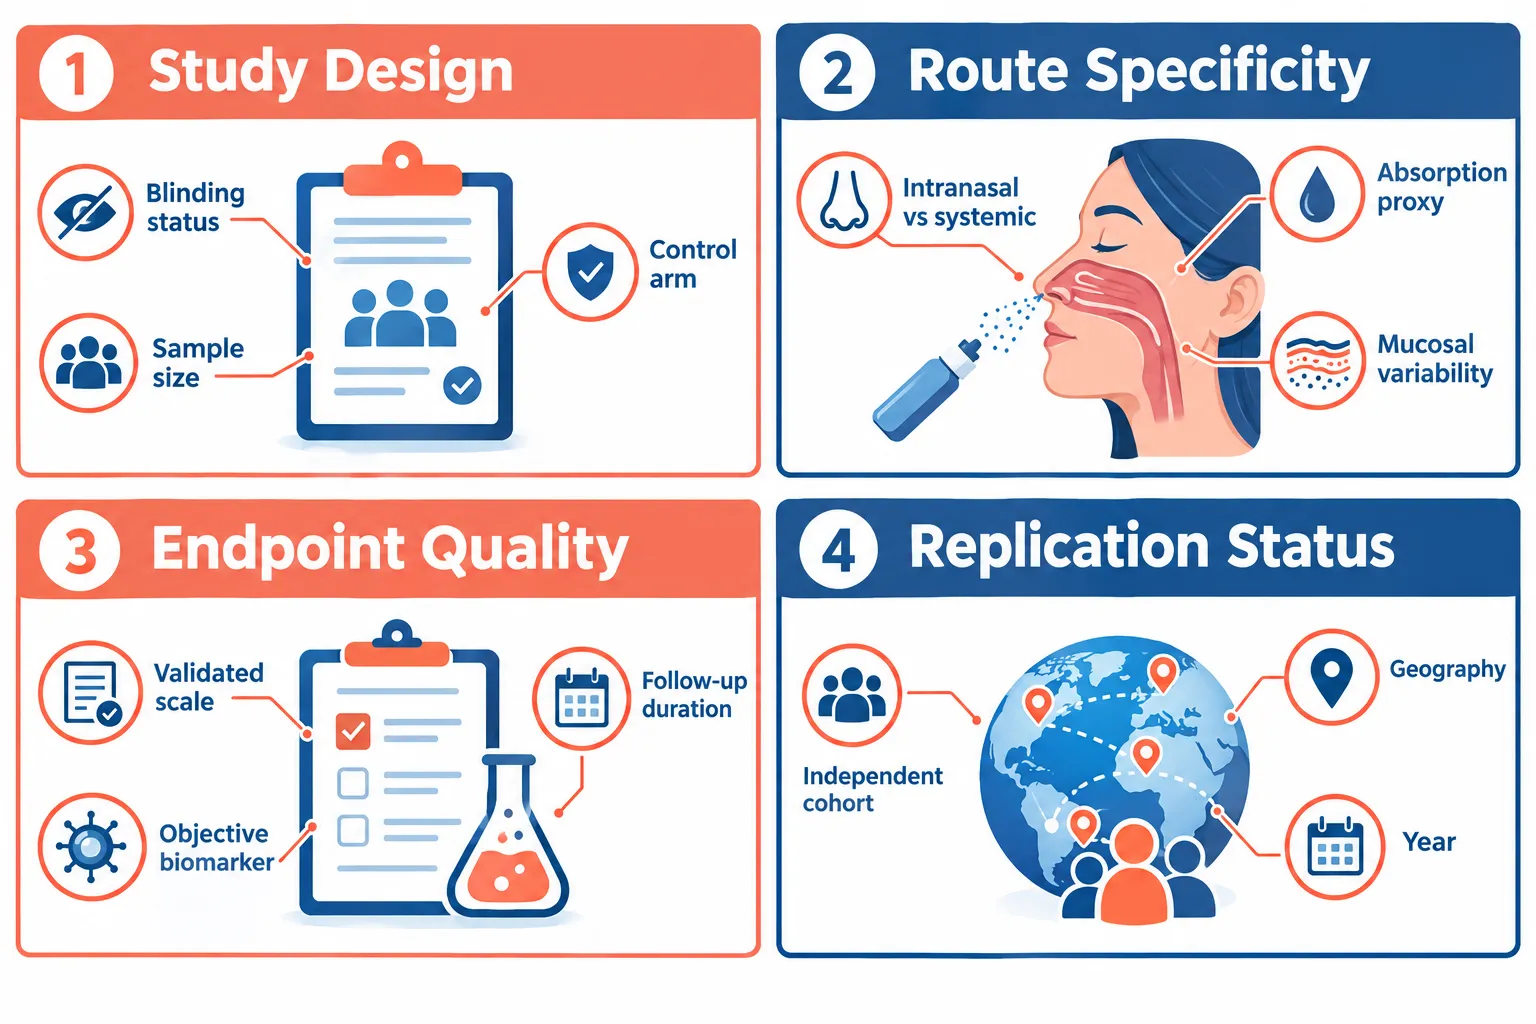
The following four-domain framework reflects emerging reviewer practice for compounds like Semax where intranasal delivery is central to the therapeutic claim.

Domain 1: Study Design Quality

Assess blinding status, randomization method, sample size, and control arm integrity. For Semax trials, most existing studies score poorly here. Single-arm or unblinded designs cannot isolate placebo effects, which are particularly strong in neurological and cognitive endpoints.

Domain 2: Route-Specific Exposure Confidence

This is the domain most commonly underweighted. Ask: does the study confirm that the intranasal dose produced a measurable, consistent exposure? If no human PK data exist, no bioavailability estimate, no Tmax, no Cmax, then exposure confidence must be rated as very low, regardless of the observed effect size.

For researchers also evaluating other intranasal peptide formats, the same logic applies when reviewing products like GLP nasal spray or ipamorelin spray formulations. The route-specific PK question is universal across intranasal peptide research.

Domain 3: Endpoint Quality and Clinical Relevance

Validated scales carry more weight than composite or investigator-defined scores. Objective biomarkers (BDNF assay, imaging) carry more weight than subjective functional ratings. Follow-up duration matters: short follow-up cannot capture delayed or sustained effects.

Domain 4: Replication and Independence

Has the finding been reproduced by an independent group, in a different country, using a different patient population? For Semax, the honest answer in 2026 is: rarely. This domain alone would push the overall evidence grade to low or very low certainty under most established grading systems.

Applying the framework produces a structured output:

  • High certainty: meets all four domains adequately
  • Moderate certainty: one domain with significant weakness
  • Low certainty: two or more domains with significant weakness
  • Very low certainty: PK domain rated as absent plus one additional domain failure

Under this schema, the current Semax intranasal evidence base grades as low to very low certainty, a conclusion consistent with expert consensus in 2026.

For those interested in how similar grading challenges apply to other research-grade peptide formulations, the analysis of research-grade peptide purity and compatibility offers a parallel methodological perspective.


Conclusion

The central challenge of evaluating Semax nasal spray in 2026 is not a shortage of reported effects, it is the absence of the mechanistic foundation needed to interpret those effects with confidence. Human pharmacokinetic data for the intranasal route remain essentially unavailable, and without them, even well-intentioned clinical signals cannot be graded above low certainty.

Actionable next steps for researchers and reviewers:

  1. Apply a route-specific PK domain explicitly when grading intranasal peptide evidence, do not fold it into general limitations.
  2. Treat single-country, unblinded trial data as hypothesis-generating only, not as confirmatory evidence.
  3. Require independent replication across at least two regulatory environments before elevating any intranasal Semax finding above low certainty.
  4. Advocate for prospective human PK studies as a prerequisite for any future regulatory submission, without them, regulatory progress remains unlikely regardless of effect size reported in existing trials.
  5. When reviewing combination-use patterns, assess each compound's intranasal PK gap independently rather than assuming shared route characteristics.

The evidence gap is real, but it is also addressable. Structured grading frameworks make that gap visible, and visibility is the first step toward closing it.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/semax-nasal-spray-in-2026-how-to-grade-intranasal-evidence-when-pharmacokinetic.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-15 13:06:452026-10-15 13:06:45Semax Nasal Spray in 2026: How to Grade Intranasal Evidence When Pharmacokinetic Data Are Missing
Intranasal Peptide Research Methods: Deposition, Mucosal Permeability, Excipient Controls, and Brain-Exposure Questions

Intranasal Peptide Research Methods: Deposition, Mucosal Permeability, Excipient Controls, and Brain-Exposure Questions

September 25, 2026/0 Comments/in Uncategorized/by

Fewer than 5% of intranasal peptide doses typically reach systemic circulation when compared with subcutaneous injection, yet the same formulation can produce measurably higher brain concentrations than an intravenous dose of the identical compound. That apparent paradox sits at the heart of modern intranasal peptide research methods: deposition, mucosal permeability, excipient controls, and brain-exposure questions, and it explains why researchers studying peptides such as Semax, Selank, and related neuropeptide formulations need a rigorous, method-specific framework rather than generic pharmacokinetic assumptions.

Key Takeaways

  • Nasal deposition, mucosal absorption, and brain exposure are three distinct, measurable variables that must be characterized separately in any intranasal peptide program.
  • Device geometry and actuation parameters govern whether a peptide deposits in the olfactory zone (relevant to nose-to-brain transport) or the lower turbinates (relevant to systemic absorption).
  • Peptide molecular weight is the strongest single predictor of intranasal systemic bioavailability; peptides under 1 kDa can achieve meaningful absorption, while larger peptides require excipient support.
  • Excipient selection drives both permeability and safety outcomes; regulatory expectations now include cilia function assays and nasal histopathology for any formulation using permeation enhancers.
  • Translating animal nose-to-brain pharmacokinetic data to human CNS exposure remains the field's most significant unsolved methodological problem as of 2026.

Mapping Nasal Deposition: Why Region Matters

Mapping Nasal Deposition: Why Region Matters

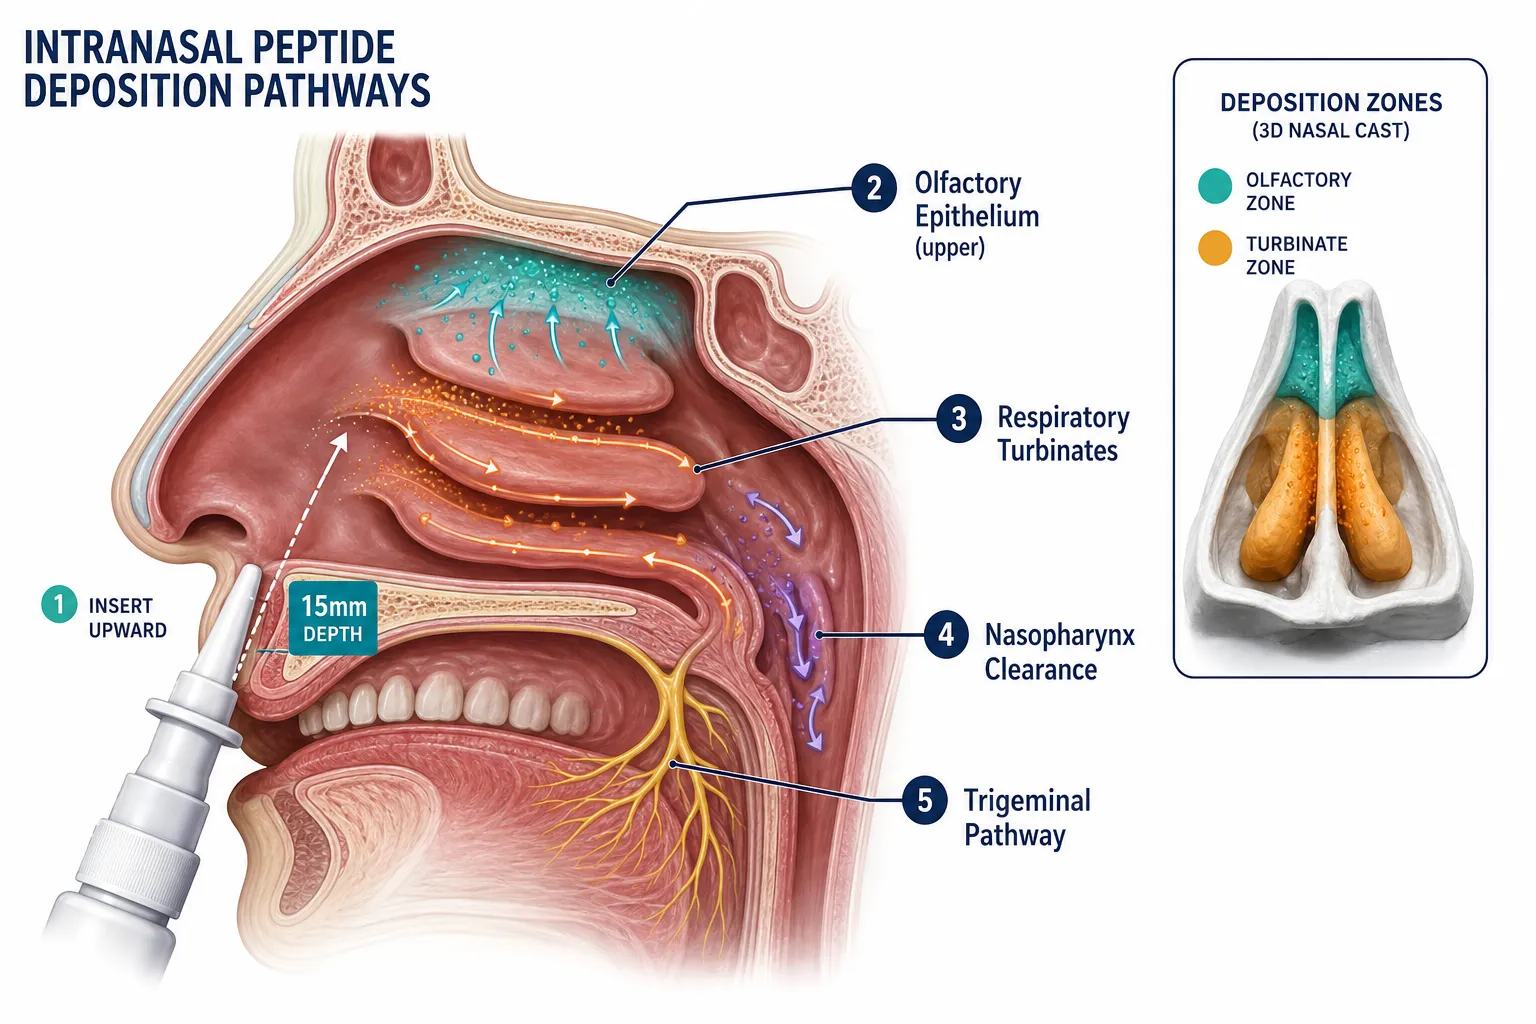
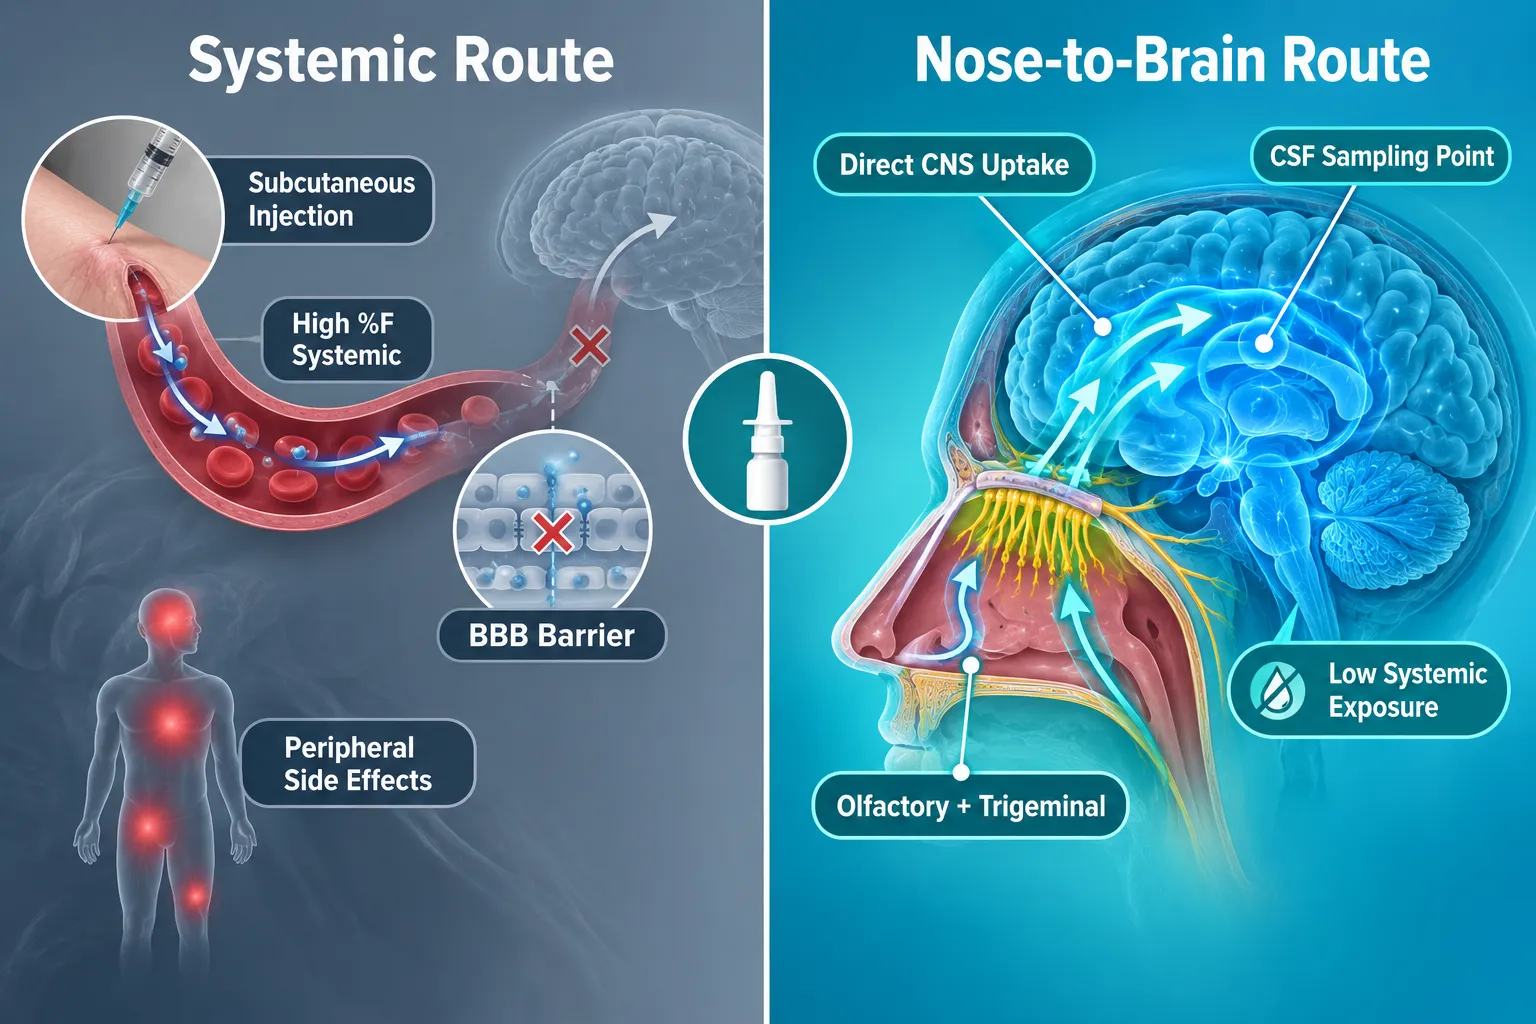
The nasal cavity is not a uniform surface. It divides functionally into a lower respiratory region lined with ciliated columnar epithelium and an upper olfactory region that connects directly to the olfactory bulb and, via the trigeminal nerve, to deeper brain structures. For systemic delivery, the respiratory turbinates provide a large vascularized surface. For nose-to-brain targeting, the olfactory epithelium is the critical zone, and it occupies only a small fraction of the total mucosal area.

Why this distinction shapes the entire research design:

  • A peptide deposited on the lower turbinates enters mucociliary clearance within minutes, limiting contact time and absorption.
  • A peptide reaching the olfactory cleft can follow axonal or perineural transport pathways to bypass the blood-brain barrier entirely.
  • Standard commercial nasal sprays are designed for turbinate deposition; nose-to-brain programs require deliberate device selection and validated deposition confirmation.

Deposition Characterization Techniques

Researchers currently use three primary methods to map where a peptide actually lands:

Method What It Measures Key Limitation
3D-printed nasal cast + spectrophotometry Regional drug mass after zone-wise rinsing Anatomical variability across donors
Radiolabeled scintigraphic imaging Real-time deposition in living subjects Regulatory complexity, radiation exposure
Transparent replica + high-resolution imaging Spray plume mechanics linked to deposition Does not capture mucosal biology

Physics-based parametric modeling, using transparent nasal replicas and software-assisted color-mask quantification, is gaining traction as a way to predict regional deposition from device and actuation parameters without animal studies. Studies comparing six commercial spray devices at a standardized 15 mm insertion depth have shown that plume angle and droplet size alone can determine whether olfactory or turbinate deposition dominates, a finding with direct implications for any researcher selecting a delivery device for neuropeptide work.

For researchers exploring nasal spray peptide delivery formats or nasal spray with PT-141, understanding device-specific deposition profiles is a prerequisite, not an afterthought.


Mucosal Permeability and Excipient Controls

Mucosal Permeability and Excipient Controls

Once a peptide reaches the mucosal surface, absorption depends on molecular weight, lipophilicity, enzymatic stability, and the formulation's excipient profile. Molecular weight is the dominant variable for systemic bioavailability: peptides under approximately 1 kDa (roughly ten amino acids or fewer) can achieve meaningful intranasal absorption without excipient support, while larger peptides show steep declines in fractional absorption unless carriers or enhancers are used.

"The inverse relationship between peptide molecular weight and intranasal bioavailability is among the most reproducible findings in nasal pharmacokinetics, and among the most frequently ignored in early-stage formulation decisions."

Excipient Classes and Their Functions

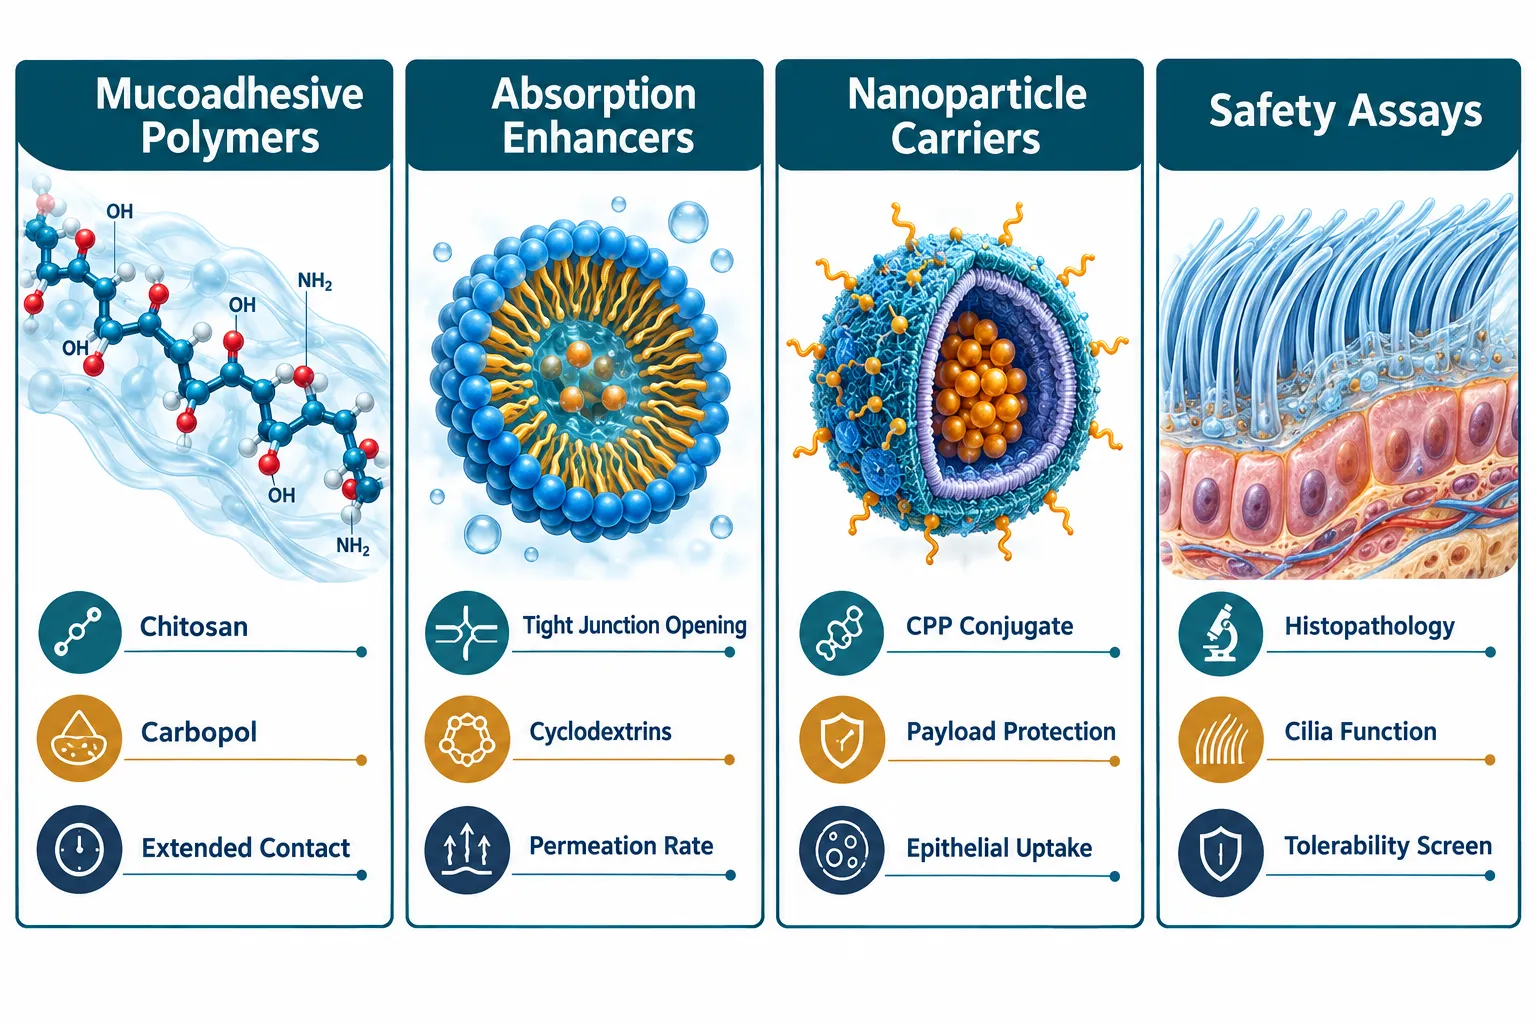
Mucoadhesive polymers such as chitosan and carbopol extend mucosal contact time, slowing mucociliary clearance and increasing the window for absorption. Chitosan also acts as a mild permeation enhancer by transiently loosening tight junctions between epithelial cells.

Cyclodextrins improve peptide solubility and protect against enzymatic degradation at the mucosal surface, which is rich in proteases.

Surfactants and absorption enhancers open paracellular routes more aggressively but carry a corresponding mucosal safety burden.

Polymeric nanoparticles and cell-penetrating peptide (CPP) conjugates represent the most advanced tier, enabling intracellular transport across the epithelial layer. Despite promising animal data, no nanoparticle-based nose-to-brain system had reached clinical trial stage as of early 2026, underscoring the translational gap.

Safety and Regulatory Expectations

Regulatory agencies now expect a defined safety package for any formulation using permeation enhancers or novel excipients:

  • Nasal mucosal histopathology (acute and chronic exposure)
  • Cilia beat frequency and morphology assays
  • Local tolerability studies at the intended dose frequency
  • Reversibility data for any observed mucosal changes

Researchers working with peptides that require enhanced permeability, including those studying peptide dosing protocols or evaluating formulation strategies for compounds like those discussed in SS-31 mechanism and research, should build mucosal safety endpoints into study design from the outset rather than treating them as late-stage add-ons.


Brain-Exposure Questions: Separating CNS from Systemic Pharmacokinetics

Brain-Exposure Questions: Separating CNS from Systemic Pharmacokinetics

The most methodologically complex aspect of intranasal peptide research methods is quantifying brain exposure independently of systemic exposure. The two are not equivalent, and conflating them produces misleading conclusions.

The core distinction:

  • Systemic bioavailability (%F) measures the fraction of the dose entering general circulation, typically assessed via plasma concentration-time curves referenced against subcutaneous or intravenous dosing.
  • Brain exposure is best measured directly via cerebrospinal fluid (CSF) sampling or brain tissue analysis in animal models, and cannot be reliably inferred from plasma data for nose-to-brain programs.

Intranasal GLP-1/GIP dual agonist peptides, intranasal insulin, and interferon-beta-1b have all demonstrated the defining pattern of nose-to-brain delivery: low systemic exposure paired with significantly elevated brain concentrations compared with intravenous or oral routes. This dichotomy is not an artifact, it reflects genuine olfactory and trigeminal transport that bypasses the blood-brain barrier.

Current Methodological Gaps

Despite consistent animal findings, several problems limit translation to human CNS pharmacokinetics:

  1. No validated in vitro model accurately replicates the human olfactory epithelium's transport characteristics.
  2. CSF sampling in humans is invasive, limiting PK characterization to sparse time points.
  3. Standardized animal paradigms for nose-to-brain transport do not yet exist, making cross-study comparisons unreliable.
  4. Anatomical scaling between rodent and human nasal geometry introduces large uncertainty when extrapolating olfactory deposition fractions.

Regulators increasingly expect quantitative deposition imaging linked to PK modeling for nose-to-brain programs, a requirement that makes early investment in nasal cast studies and CSF sampling protocols strategically necessary rather than optional. Researchers evaluating compounds with potential CNS applications, including those reviewing polypeptide peptides in cardiometabolic models or examining CJC-1295 pharmacokinetic comparisons, should treat brain-exposure quantification as a distinct study objective with its own sampling strategy.

Sourcing research-grade material with verified purity is equally foundational. Impurities in peptide formulations can confound both permeability measurements and CNS exposure data. Resources such as evaluating purity for research-grade peptide formulations offer useful frameworks for assessing supplier quality before committing material to in vivo studies.


Conclusion

A rigorous approach to intranasal peptide research requires treating nasal deposition, mucosal permeability, and brain exposure as three distinct measurement problems, not a single pharmacokinetic endpoint. The actionable steps for researchers in 2026 are clear:

  1. Select and validate the delivery device using nasal cast studies before committing to in vivo work; device geometry determines whether olfactory or turbinate deposition dominates.
  2. Match excipient strategy to peptide molecular weight; small peptides may need only mucoadhesives, while larger peptides require carriers or enhancers with a full mucosal safety package.
  3. Design separate PK endpoints for systemic and CNS exposure; do not infer brain concentrations from plasma data in nose-to-brain programs.
  4. Incorporate standardized deposition metrics early, as regulatory expectations for quantitative imaging linked to PK modeling are rising across the field.
  5. Source verified, research-grade peptide material to ensure that formulation variables, not impurity profiles, drive experimental outcomes.

The nose-to-brain route offers genuine advantages for neuropeptide research, but those advantages are only accessible through disciplined, method-specific study design.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/intranasal-peptide-research-methods-deposition-mucosal-permeability-excipient-co.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-25 13:03:542026-09-25 13:03:54Intranasal Peptide Research Methods: Deposition, Mucosal Permeability, Excipient Controls, and Brain-Exposure Questions
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top