Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework
{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Spironolactone and GLP or Growth-Hormone' in crisp white sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins, two balanced lines, no character near any edge. Background: clean editorial medical illustration showing kidney cross-section with aldosterone signaling arrows, potassium ion symbols, and molecular structure silhouettes in teal and gold on a dark navy field. Magazine-quality medical editorial aesthetic, high contrast, pharmaceutical research tone.","content":["Annotated mechanism-of-action diagram, landscape format (1536×1024), showing the mineralocorticoid receptor pathway in the distal convoluted tubule: four labeled stages left to right, 'Aldosterone Binds Receptor', 'Spironolactone Blocks Site', 'Sodium Excretion Rises', 'Potassium Retained', with thin callout arrows pointing to each stage, illustrated cross-section of renal tubule cells in center, teal-and-white palette on a light gray background, clean medical editorial style, no pricing or checkmarks.","Three-panel labeled comparison guide, landscape format (1536×1024), comparing potassium monitoring timelines: Panel 1 labeled 'Week 1 Check' showing a blood draw vial icon with '5.0 mmol/L threshold' callout; Panel 2 labeled 'Monthly x3 Months' with a calendar icon and 'Creatinine + K+' callout; Panel 3 labeled 'Quarterly Then 6-Monthly' with a line graph icon and 'Renin Target' callout. Navy, teal, and amber palette on white background, clinical infographic style, bold panel headings, short bullet labels only.","Split-screen editorial illustration, landscape format (1536×1024): left half shows a GLP-1 receptor agonist pathway diagram with labeled nodes, 'Incretin Effect', 'Plasma Volume Drop', 'NT-proBNP Reduction', 'Weight Loss', connected by flow arrows in green and slate; right half shows a spironolactone aldosterone-blockade pathway with labeled nodes, 'MRA Blockade', 'Fluid Offloading', 'BP Normalization', 'K+ Rise Risk', in teal and navy. Center dividing line with label 'Integrated Cardiometabolic Framework'. Clean white background, bold callout lines, medical editorial polish.","Numbered step-by-step process flow diagram, landscape format (1536×1024), showing five horizontal stages of a combined spironolactone plus GLP-peptide monitoring protocol: Step 1 'Baseline Labs: K+, eGFR, Renin, Aldo'; Step 2 'Start or Titrate Spiro'; Step 3 'Day 3-5: Adjust K+ Supplements'; Step 4 'Week 1: Recheck K+ and Creatinine'; Step 5 'Month 2-3: Reassess Renin, NT-proBNP'. Each step in a rounded card, connected by bold directional arrows, teal-to-navy gradient across cards, amber warning badge on Step 4, clean sans-serif labels, white background, clinical protocol aesthetic."]

Fewer drugs in clinical medicine carry as many overlapping metabolic consequences as spironolactone, a potassium-sparing diuretic that simultaneously lowers blood pressure, reshapes fluid distribution, and alters how every co-administered agent affects renal electrolyte handling. As research into GLP-1 receptor agonists and growth-hormone peptides expands into cardiometabolic territory, the intersection with mineralocorticoid receptor antagonism (MRA) has become impossible to ignore. Understanding the Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework is increasingly essential for clinicians and researchers navigating this overlapping landscape.
Key Takeaways
- Spironolactone competitively blocks aldosterone at the distal tubule, raising serum potassium and reducing sodium and water retention, effects that require structured laboratory monitoring.
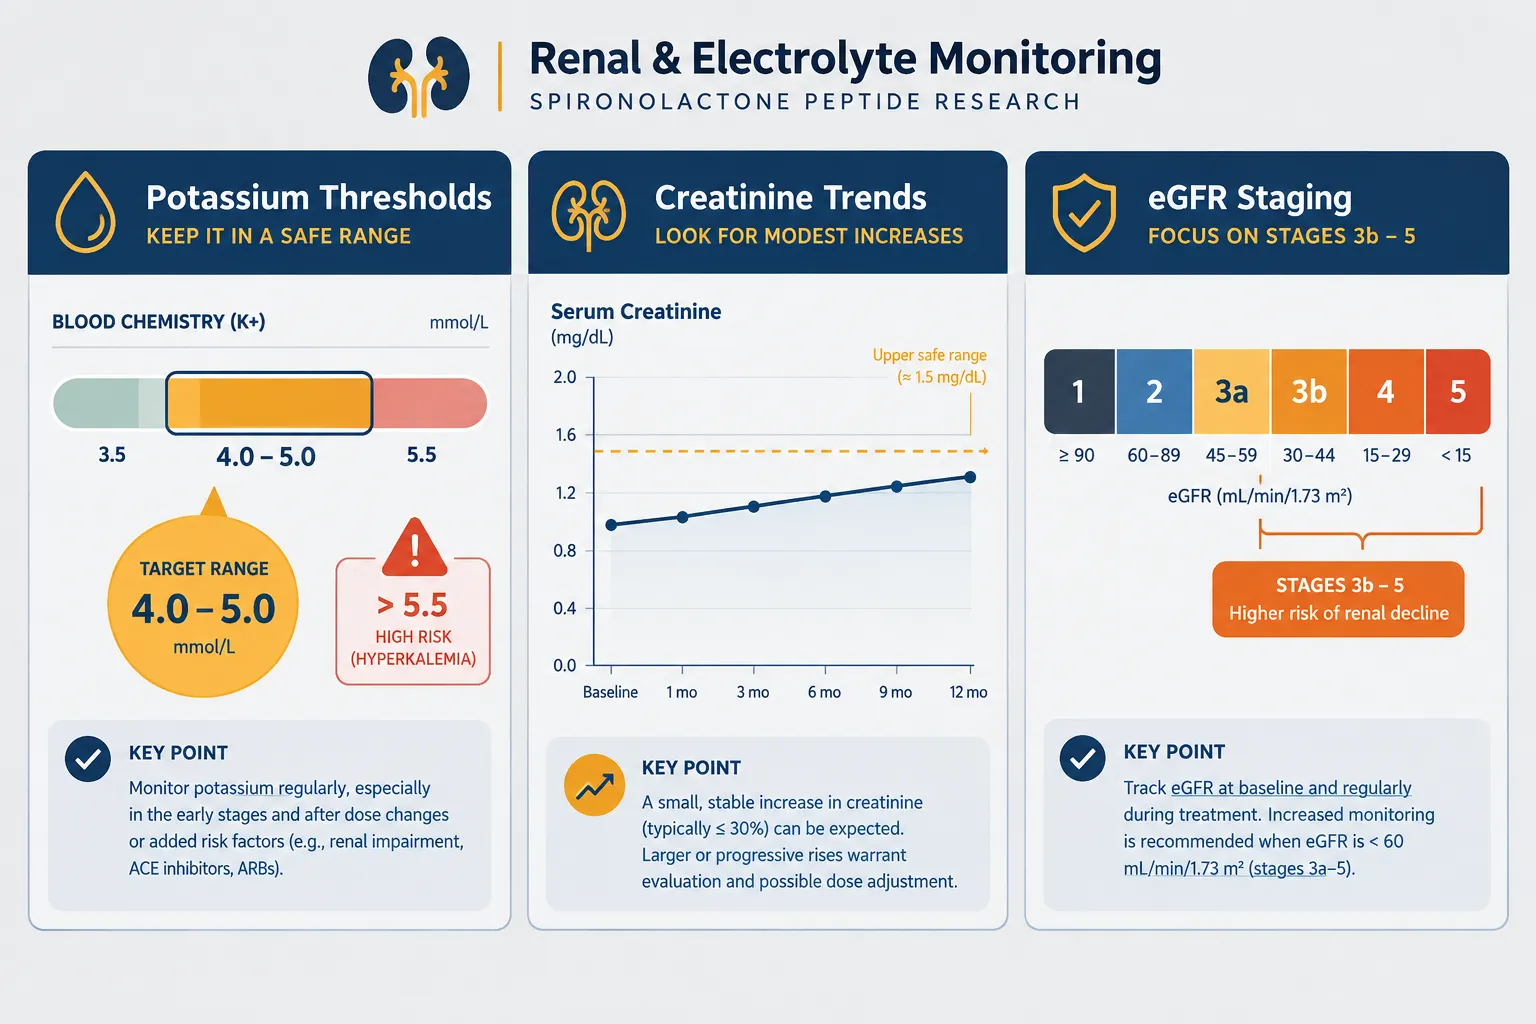
- Potassium must be checked within one week of starting or up-titrating spironolactone, then monthly for three months, quarterly for a year, and every six months thereafter.
- GLP-1 and dual incretin agonists produce early plasma volume reductions and NT-proBNP decreases that can compound or mask fluid changes from mineralocorticoid blockade.
- No formal co-therapy guideline currently covers combined spironolactone and GLP or growth-hormone peptide use; any integrated framework is built by extrapolating from MRA, primary aldosteronism, and heart failure evidence.
- Renin is the primary biochemical titration target for spironolactone in aldosterone-excess states; potassium serves as both a safety marker and a key interpretive variable.
How Spironolactone Changes Aldosterone, Potassium, and Fluid Status
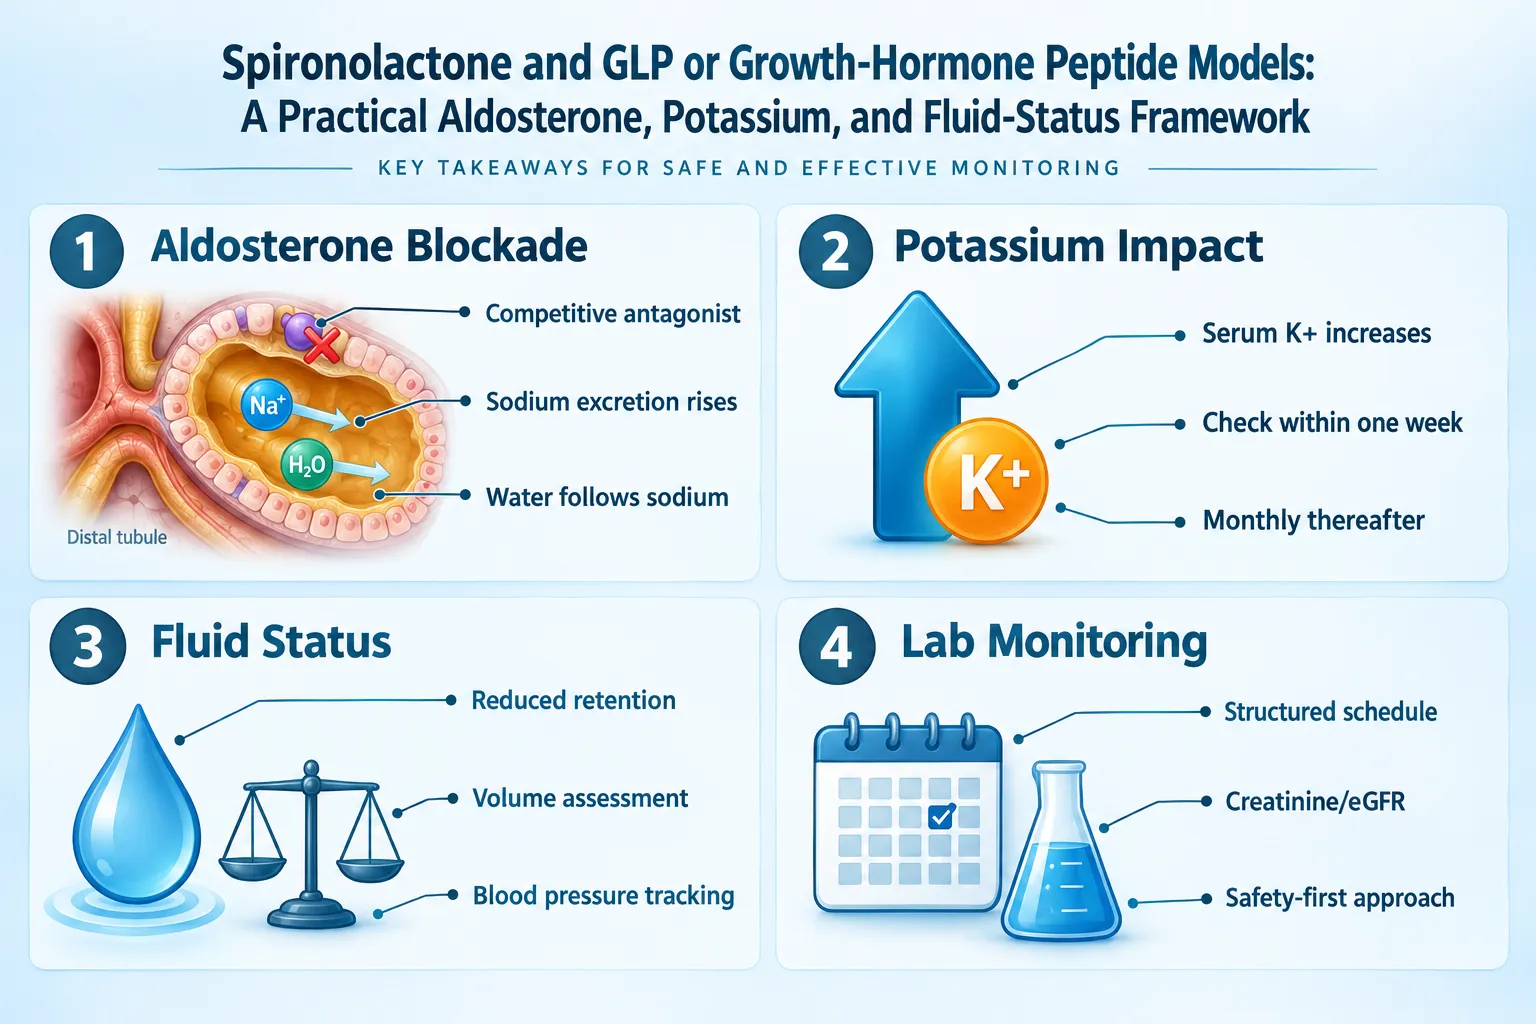
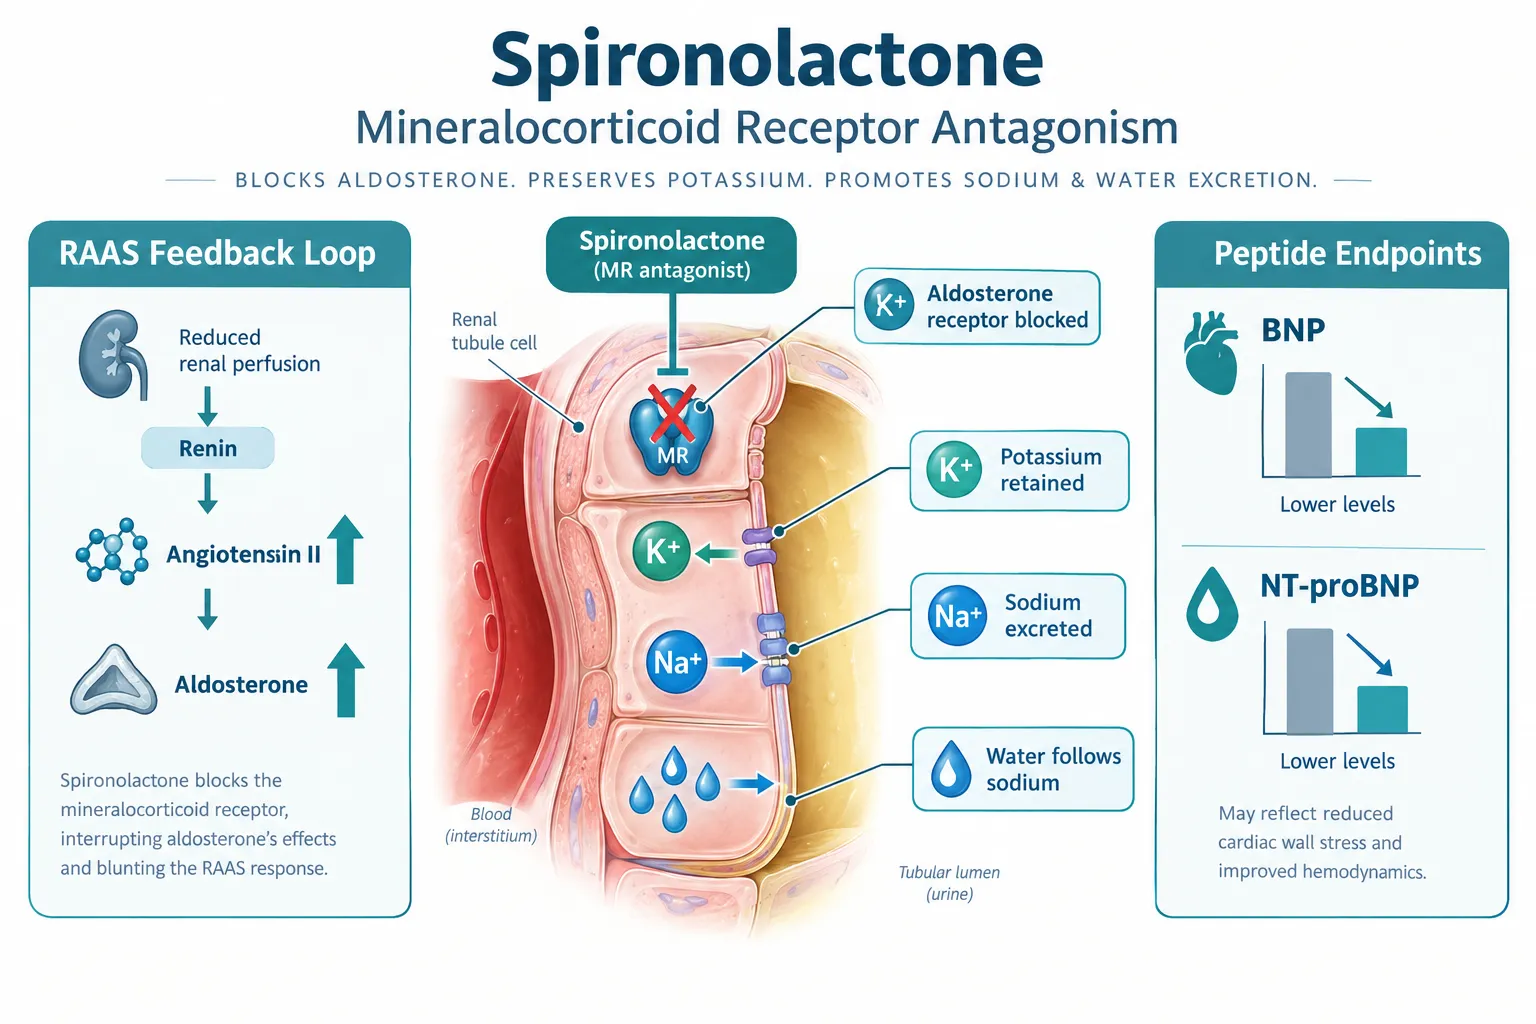
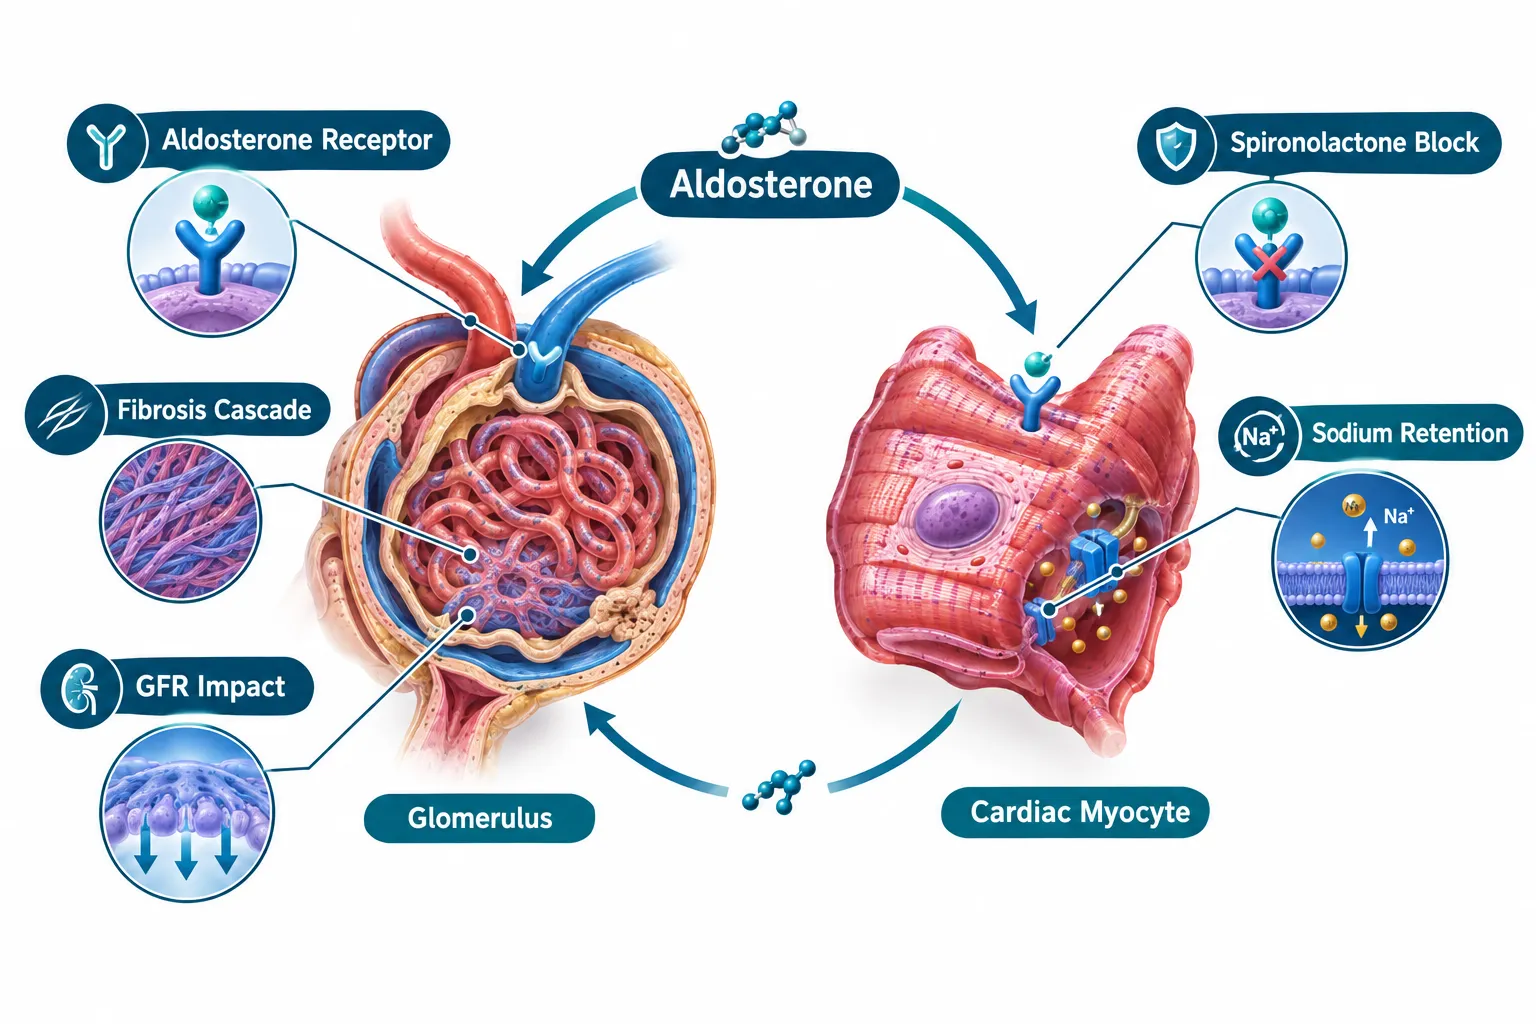
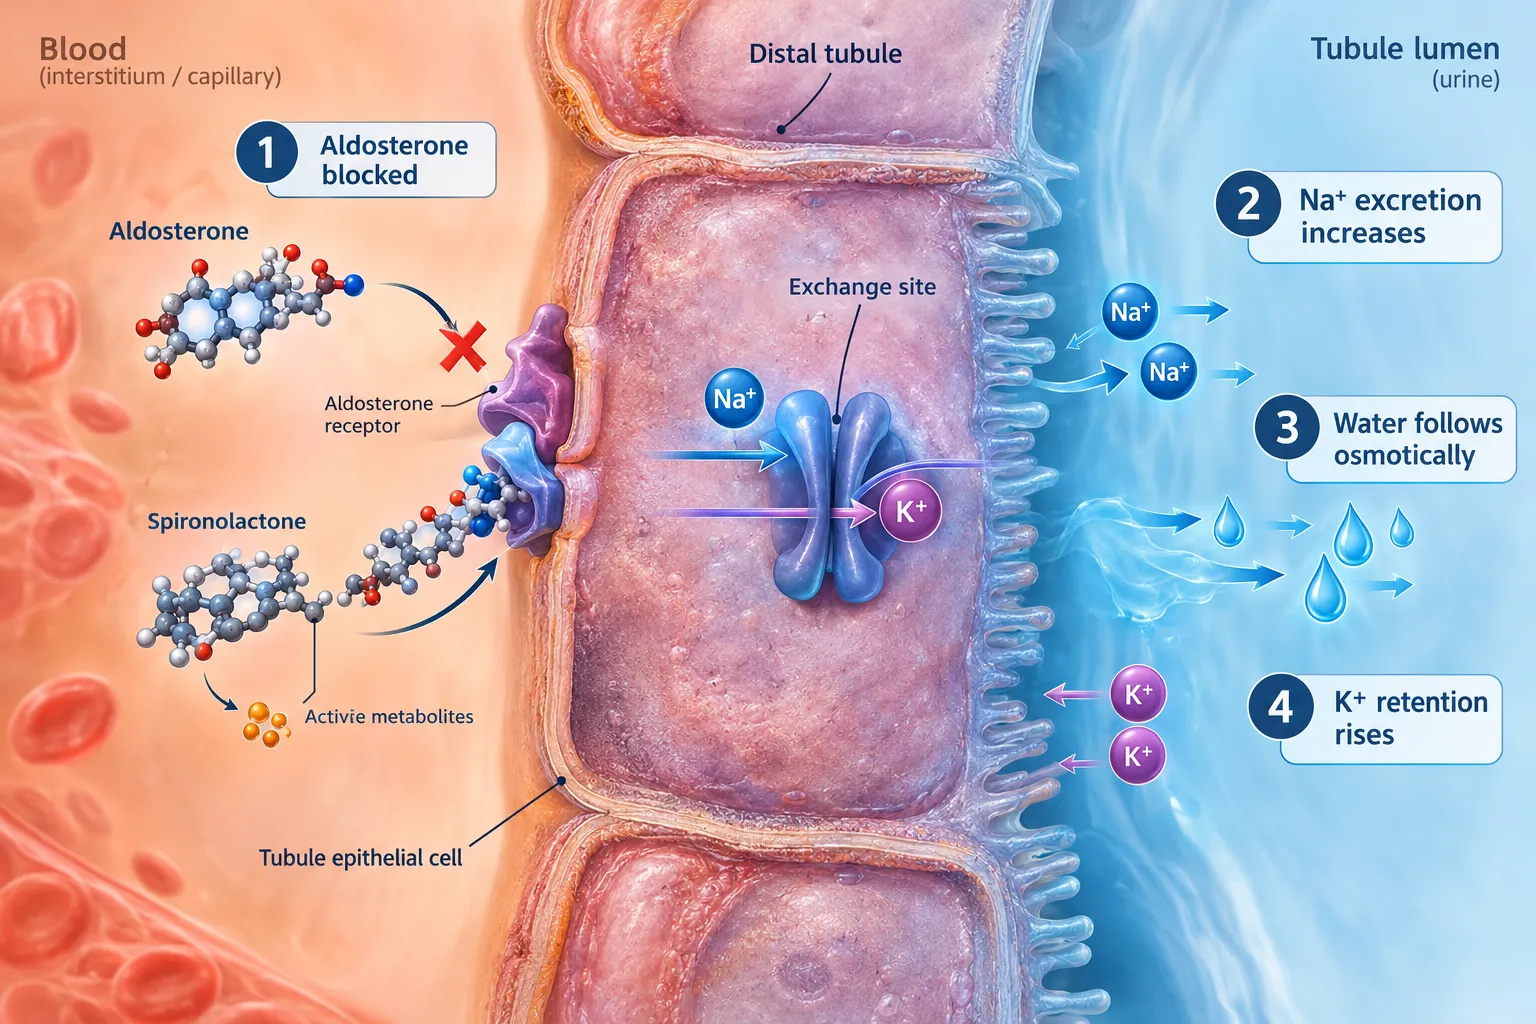
Spironolactone's pharmacology is specific and mechanistically clean. It and its active metabolites act as competitive antagonists at the aldosterone-dependent sodium-potassium exchange site in the distal convoluted tubule. When aldosterone is blocked, sodium excretion rises, water follows, and, critically, potassium is retained rather than excreted.
This mechanism explains why the drug is first-line medical therapy for primary aldosteronism, resistant hypertension, and heart failure with reduced ejection fraction. In aldosterone-excess states, starting spironolactone at 12.5-25 mg daily with careful titration typically normalizes serum potassium within three to five days. That rapid shift means potassium supplements already being taken by the patient often need reduction or discontinuation by days two to four to prevent rebound hyperkalemia.
Why Potassium Is Both a Safety Marker and a Diagnostic Variable
Potassium's role in a spironolactone framework goes beyond safety. Low serum potassium can artificially lower measured aldosterone, potentially misleading diagnosis or obscuring the true degree of aldosterone excess. As a result, potassium must be corrected and then tracked alongside renin and aldosterone throughout therapy, not just checked once at baseline.
The treatment target in primary aldosteronism is an unsuppressed renin, which signals adequate mineralocorticoid receptor blockade. This renin-centered titration strategy is a cornerstone of the broader Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework when applied to aldosterone-driven conditions.
"Renin normalization is the biochemical proof of adequate mineralocorticoid blockade, potassium is the safety guardrail."
The Monitoring Schedule That Anchors Any Practical Framework
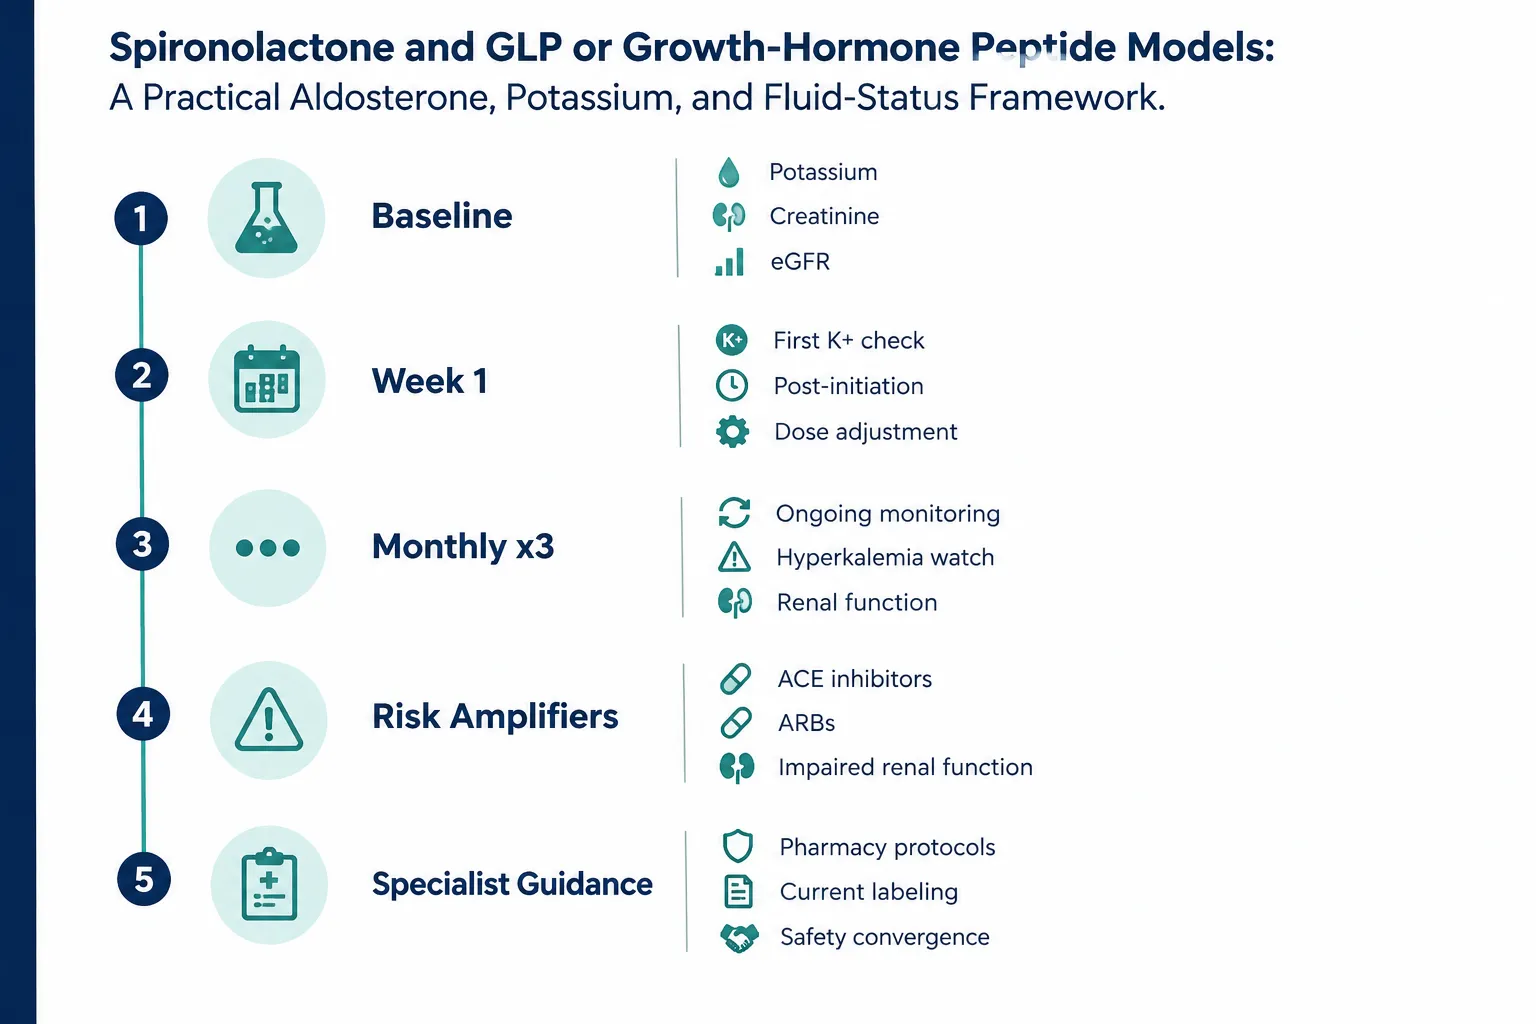
Hyperkalemia is the central safety concern with spironolactone. Risk amplifies with impaired renal function, concurrent ACE inhibitors, ARBs, and any agent that independently raises potassium. Current labeling and specialist pharmacy guidance converge on a structured monitoring schedule:
| Timepoint | Parameters to Check |
|---|---|
| Baseline | Potassium, creatinine/eGFR, blood pressure, renin, aldosterone |
| 1 week after starting or dose change | Potassium, creatinine |
| Monthly for first 3 months | Potassium, creatinine |
| Every 3 months, months 3-12 | Potassium, creatinine |
| Every 6 months thereafter | Potassium, creatinine |
| 2-3 months after initiation | Renin (to assess titration adequacy) |
Action thresholds are equally important:
- Potassium above 5.0 mmol/L at baseline: spironolactone is contraindicated.
- Potassium 5.5-6.0 mmol/L during therapy: reduce dose or hold temporarily.
- Potassium above 6.5 mEq/L: emergency intervention required.
- Creatinine above approximately 4 mg/dL: consider discontinuation.
This schedule forms the operational backbone of any aldosterone, potassium, and fluid-status model regardless of what co-therapies are layered on top.
Where GLP and Growth-Hormone Peptide Models Intersect
The connection between incretin-based therapies and spironolactone is not arbitrary. A 2026 network meta-analysis on obstructive sleep apnea found both spironolactone and the dual GLP-1/GIP agonist tirzepatide among the most effective interventions for reducing apnea-hypopnea index, a finding that highlights converging cardiometabolic benefits across MRA and incretin pathways.
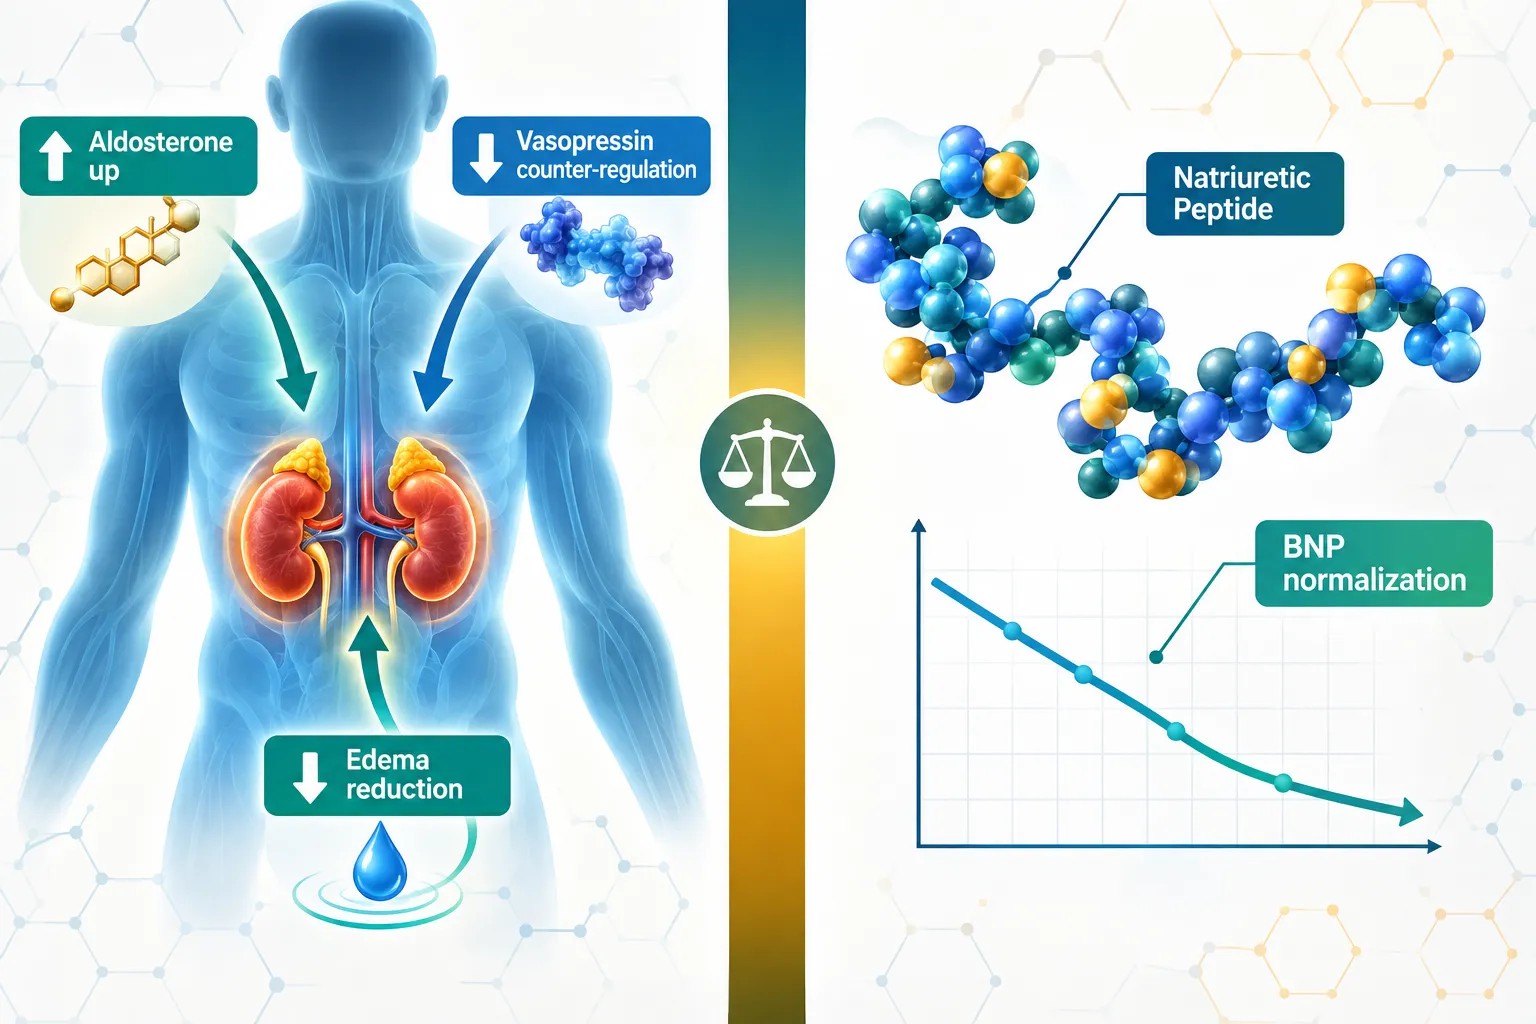
GLP-1 receptor agonists also produce measurable early reductions in plasma volume and NT-proBNP before significant weight loss occurs, suggesting cardiac-specific and potentially volume-modulating effects. When these agents run concurrently with spironolactone, several interactions become clinically relevant:
- Volume depletion risk: Both drug classes reduce fluid retention through distinct pathways. Combined use may produce greater blood pressure reduction and orthostatic symptoms than either agent alone.
- NT-proBNP interpretation: GLP-1-driven NT-proBNP reductions can obscure the fluid-status signal that clinicians use to assess heart failure trajectory on MRA therapy.
- Weight and blood pressure reassessment: Significant weight loss from GLP or growth-hormone peptide protocols reduces aldosterone secretion independently, which can shift the spironolactone dose requirement downward over time.
Research into GLP-3 peptide signaling pathways and related GLP-3 peptide products is increasingly part of this evolving framework, as investigators examine how incretin-family peptides modulate fluid and metabolic endpoints beyond classical glucoregulation. Similarly, mitochondrial-targeted agents such as the SS-31 peptide and research around SS-31 peptide benefits suggest additional cardiorenal pathways that may eventually intersect with MRA therapy in translational models.
It is important to state clearly: as of 2026, no dedicated guideline or randomized trial directly addresses a formalized protocol for combined spironolactone and GLP-1 or growth-hormone peptide co-therapy. Any integrated model must extrapolate from well-established MRA monitoring schedules, incretin-related volume data, and cardiometabolic risk frameworks.
Building a Practical Combined Protocol
A synthesized, non-official practical protocol for the Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework would include:
- Baseline panel: Blood pressure, volume status assessment, potassium, creatinine/eGFR, renin, aldosterone, NT-proBNP, and body weight before initiating or up-titrating spironolactone.
- Early potassium management: Expect potassium normalization within three to five days; reduce or stop potassium supplements by days two to four with close monitoring.
- Week-one check: Recheck potassium and creatinine; adjust dose if thresholds are approached.
- Monthly monitoring: Continue for the first three months; include symptom-based fluid assessment, weight trends, edema, orthostatic symptoms.
- Renin reassessment at two to three months: Titrate spironolactone toward an unsuppressed renin while tracking potassium and creatinine.
- GLP/peptide-specific additions: Track NT-proBNP and weight trajectory; reassess spironolactone dose if significant weight loss alters aldosterone secretion; watch for additive volume depletion.
Researchers following this area may also find value in reviewing lab-tested peptides standards and emerging data on combination agents like cagrilinitide peptide, which represents dual-mechanism incretin modulation relevant to the cardiometabolic overlap with MRA therapy.
Conclusion
The Spironolactone and GLP or Growth-Hormone Peptide Models: A Practical Aldosterone, Potassium, and Fluid-Status Framework is not yet a formal guideline construct, but the clinical need for one is real and growing. Spironolactone's well-characterized effects on aldosterone, potassium, and fluid balance provide a rigorous structural foundation. Layering GLP-1 or growth-hormone peptide effects on top requires extending that foundation to include volume-depletion vigilance, NT-proBNP trending, and weight-driven reassessment of MRA dosing.
Actionable next steps for clinicians and researchers:
- Apply the structured potassium and creatinine monitoring schedule from established MRA labeling as a non-negotiable baseline.
- Add NT-proBNP and weight trending when any incretin-class or growth-hormone peptide is co-administered.
- Reassess renin at two to three months and recalibrate spironolactone dose if body weight changes significantly.
- Treat potassium simultaneously as a safety guardrail and a diagnostic variable when interpreting aldosterone status.
- Continue monitoring the emerging literature, this intersection will likely produce dedicated guidance as GLP-based co-therapy becomes more common across cardiometabolic practice.