Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: phase 3 clinical trials

Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models

Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models

November 9, 2026/0 Comments/in Uncategorized/by

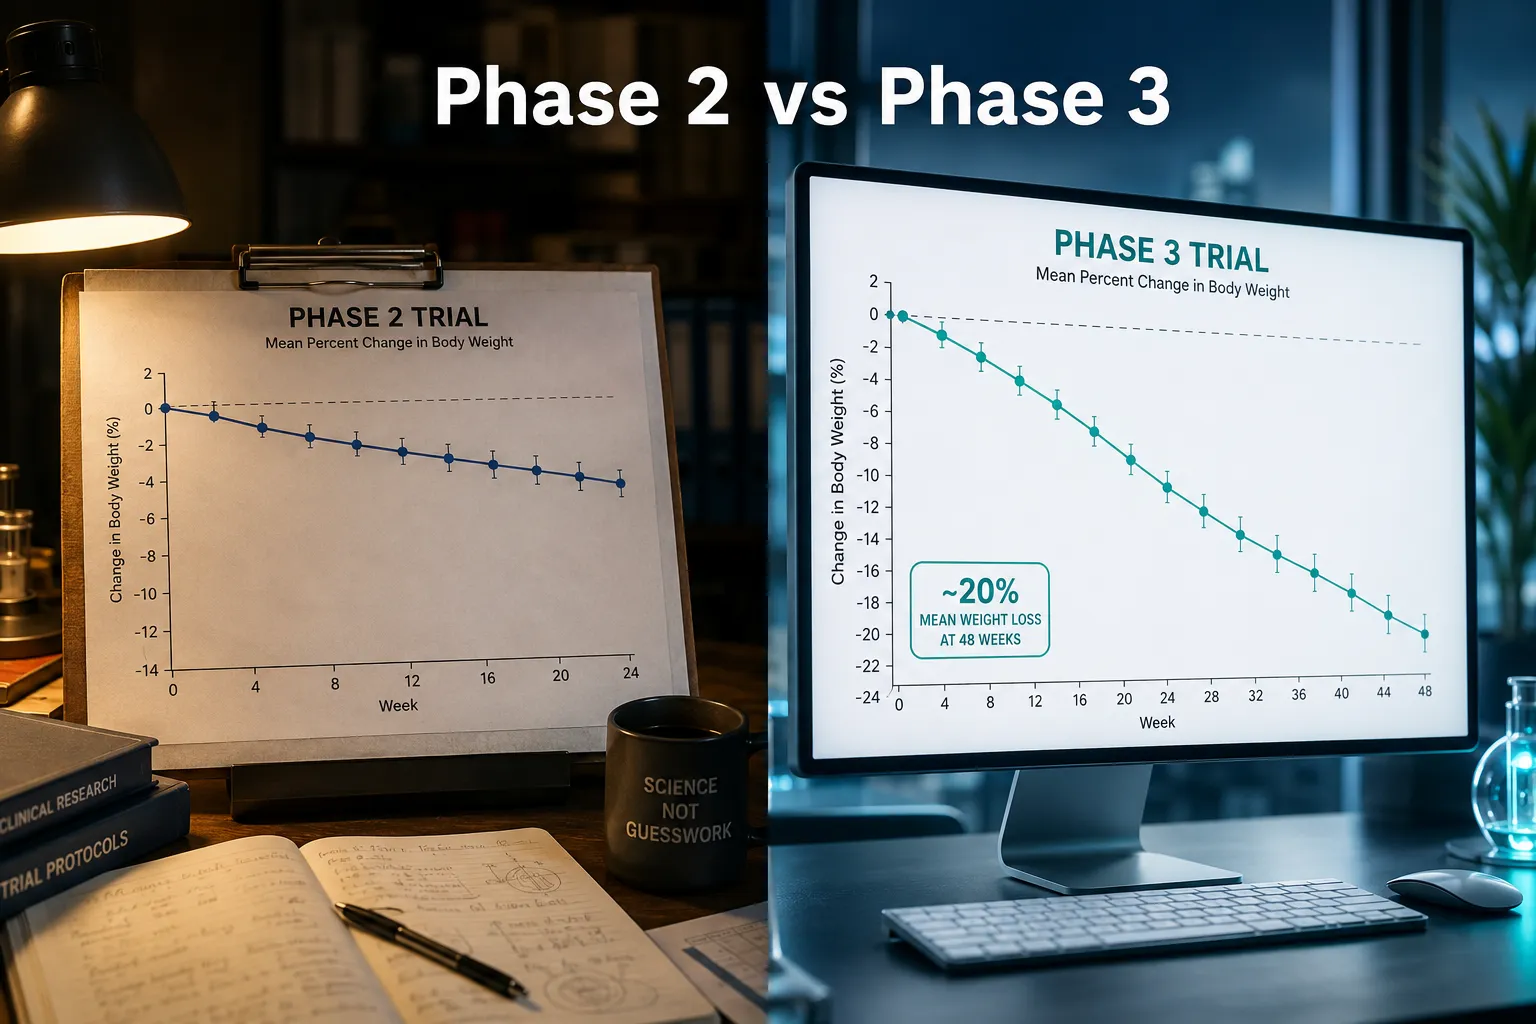
Roughly 24% mean body weight reduction at 48 weeks, that was the phase 2 signal that made retatrutide one of the most closely watched peptides in metabolic research. Now, with multiple phase 3 readouts published or presented through 2026, the question is no longer whether the triple-agonist effect is real. The question is what the Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models means for how researchers design experiments around GLP-1, GIP, and glucagon receptor signaling going forward.

Key Takeaways

  • Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, a tri-receptor profile that separates it mechanistically from earlier incretin-only agents.
  • Phase 3 TRIUMPH-1 (obesity, 80 weeks) and TRIUMPH-2 (type 2 diabetes with obesity) confirm dual metabolic endpoints at a scale phase 2 could not.
  • TRIUMPH-4 extends the evidence base to musculoskeletal outcomes, specifically knee osteoarthritis with obesity, a first for this receptor class.
  • The phase 3 portfolio now spans obesity, type 2 diabetes, cardiovascular disease, sleep apnea, MASLD, and chronic low back pain, forcing researchers to think beyond weight-loss endpoints.
  • For preclinical and translational research models, receptor-selective controls and dose-exposure titration have become essential design requirements.

What the Triple-Agonist Mechanism Demands From Research Design
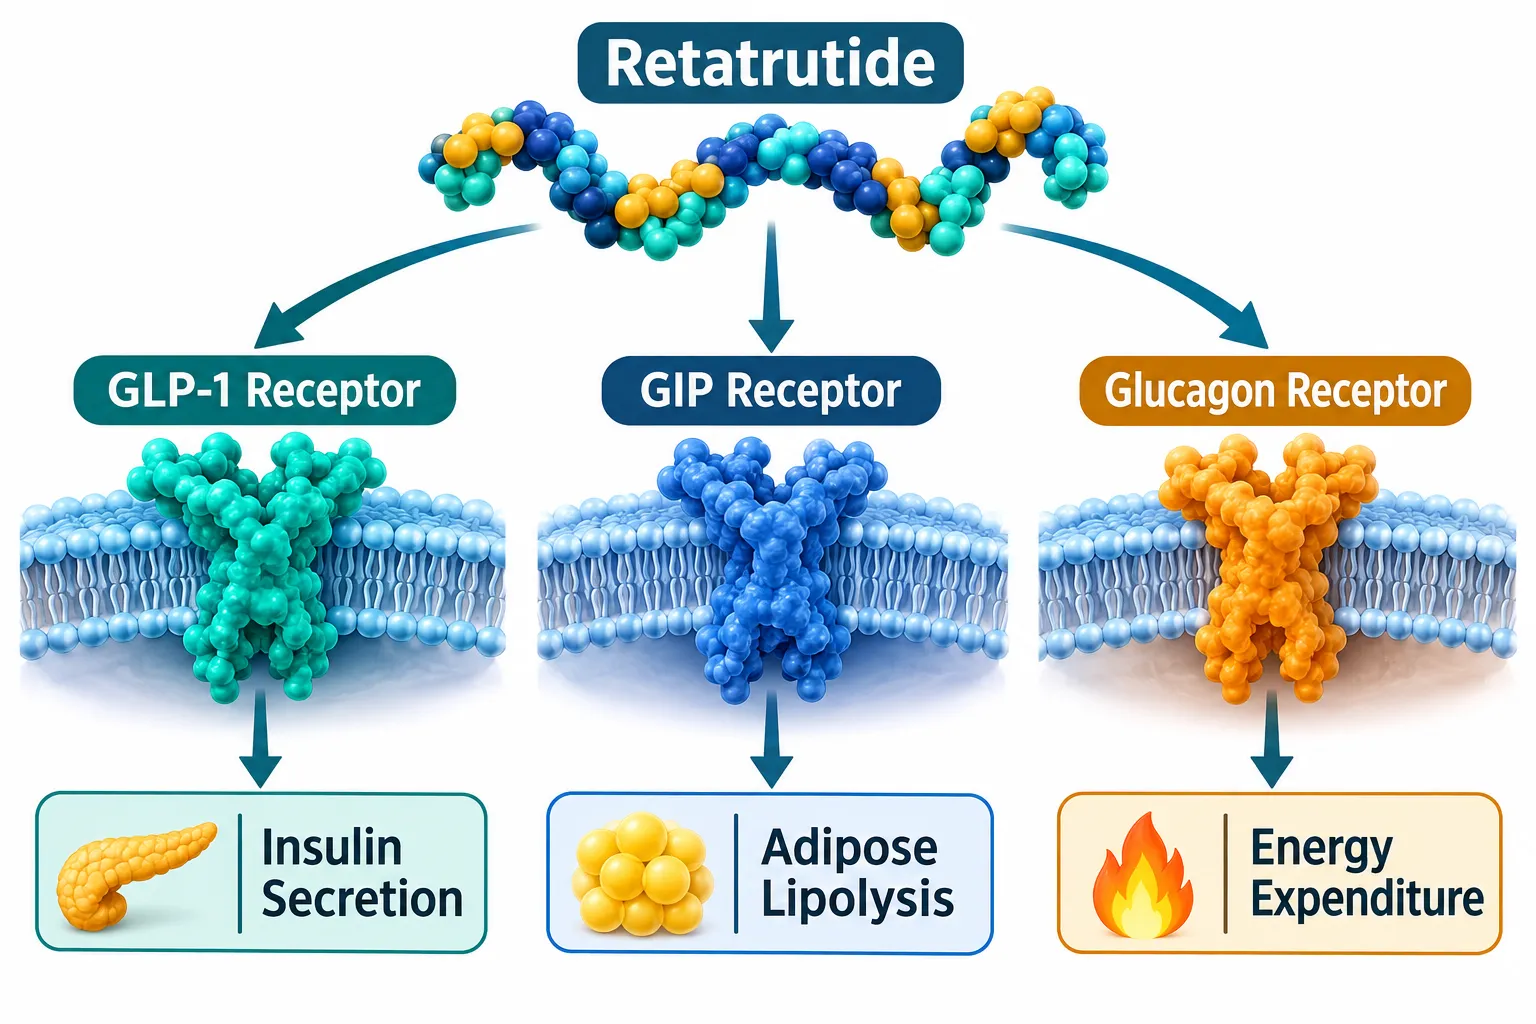
What the Triple-Agonist Mechanism Demands From Research Design

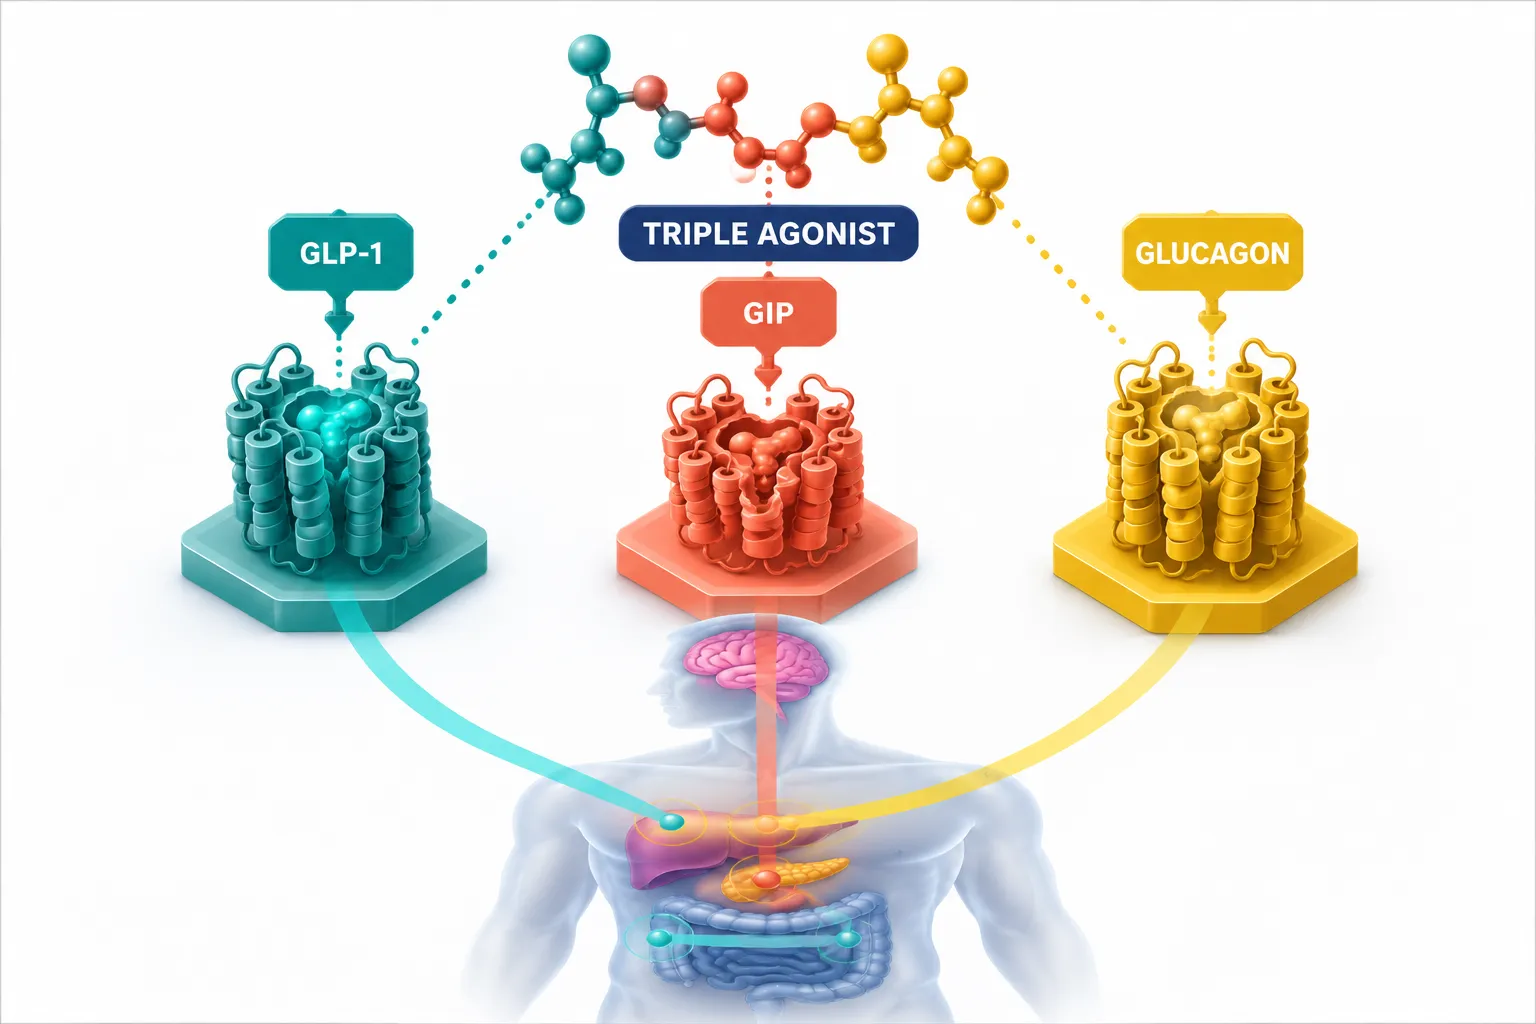
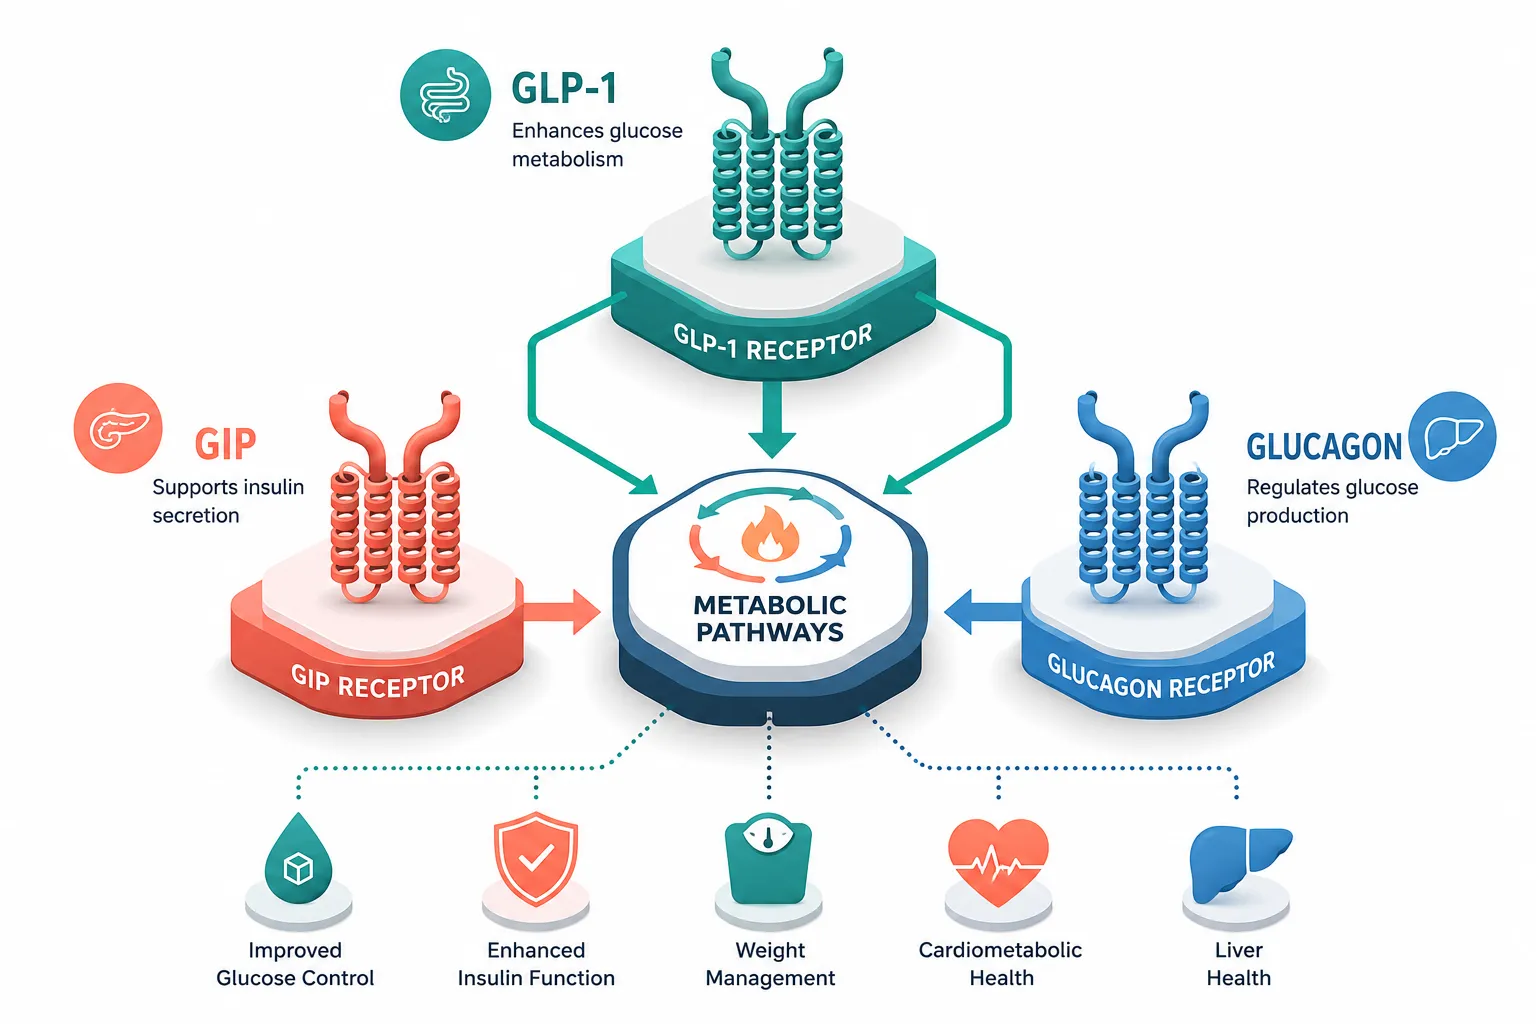
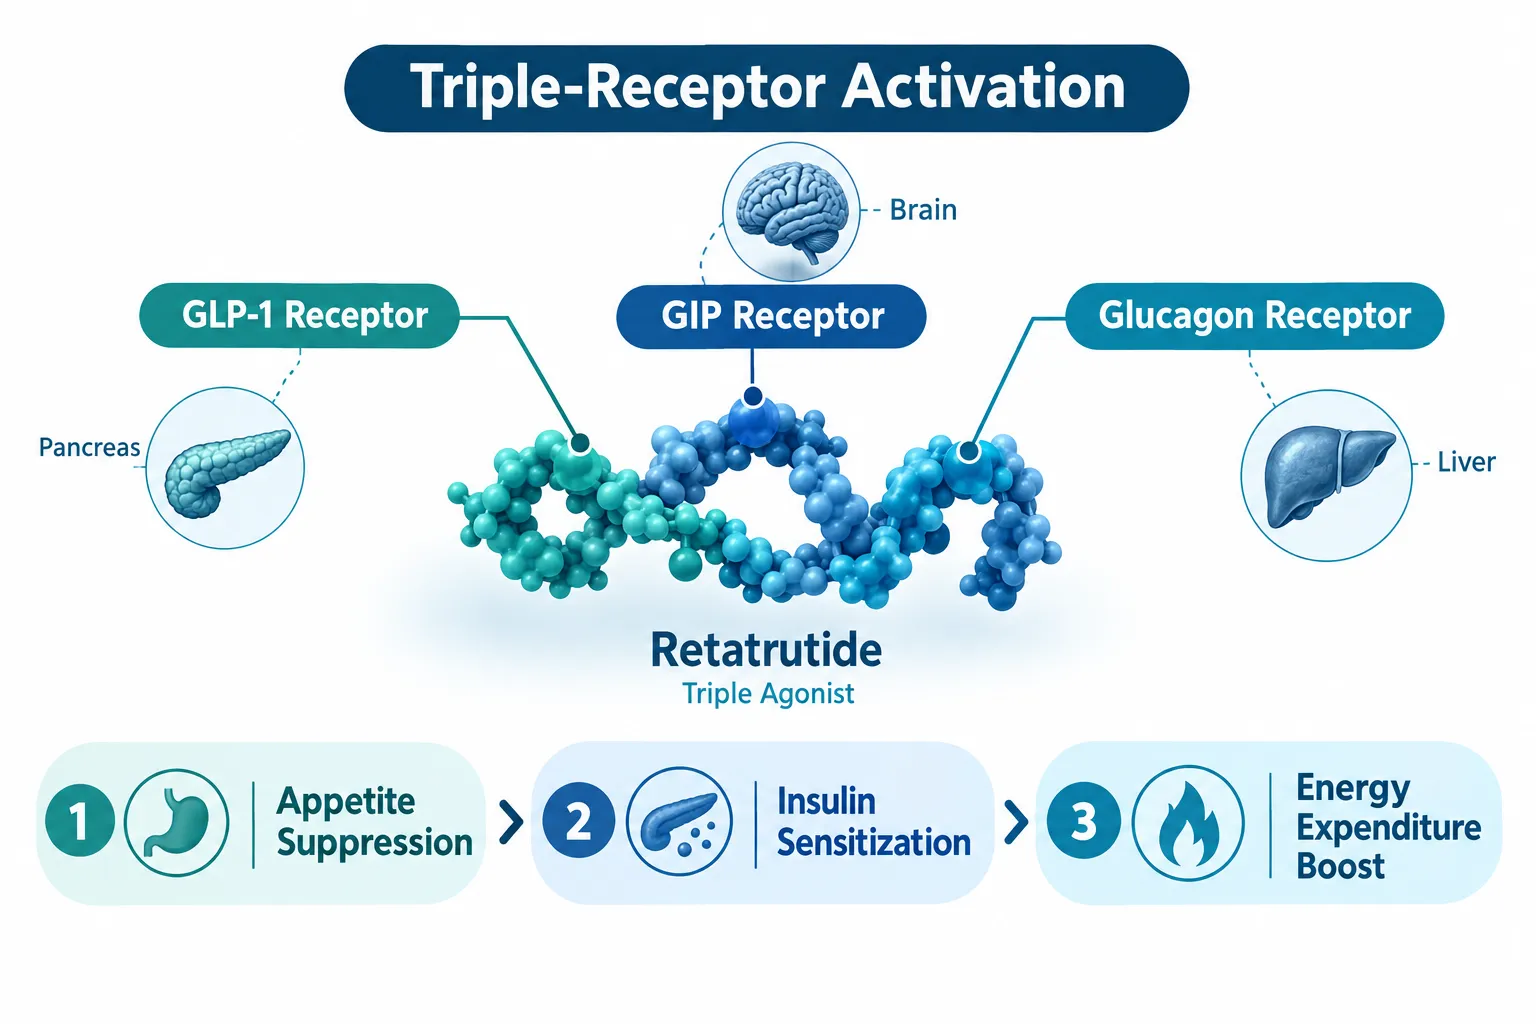
Retatrutide binds three receptors, GLP-1R, GIPR, and glucagon receptor (GCGR), simultaneously. Each receptor drives a distinct but overlapping metabolic cascade. GLP-1R activation suppresses appetite and slows gastric emptying. GIPR activation modulates adipose tissue and potentiates insulin secretion. GCGR activation increases hepatic glucose output and thermogenic energy expenditure.

This layered pharmacology is precisely what makes the Retatrutide Phase 3 Evidence Update so consequential for GLP-3 research models. When a single compound hits all three axes, attribution becomes a central methodological problem. Which portion of the observed weight loss or glycemic improvement comes from which receptor? Phase 3 trials are powered for clinical endpoints, not mechanistic dissection, so that burden falls on bench and translational research.

Key design implications:

  • Including receptor-selective agonist controls (GLP-1-only, GIP-only, GCGR-only) alongside a triple-agonist arm is now a baseline expectation in well-constructed studies.
  • Dose-exposure matching across receptor arms is non-trivial; equipotent dosing at each receptor requires careful titration rather than simple weight-based scaling.
  • Metabolic endpoint panels should capture lipid flux, hepatic glucose production, and thermogenic markers, not just body weight or fasting glucose.

Researchers exploring GLP-3 triple agonist research planning and catalog navigation should map their experimental endpoints to this receptor-specific attribution framework before committing to a protocol.


Phase 3 Trial Portfolio: What the New Evidence Base Covers
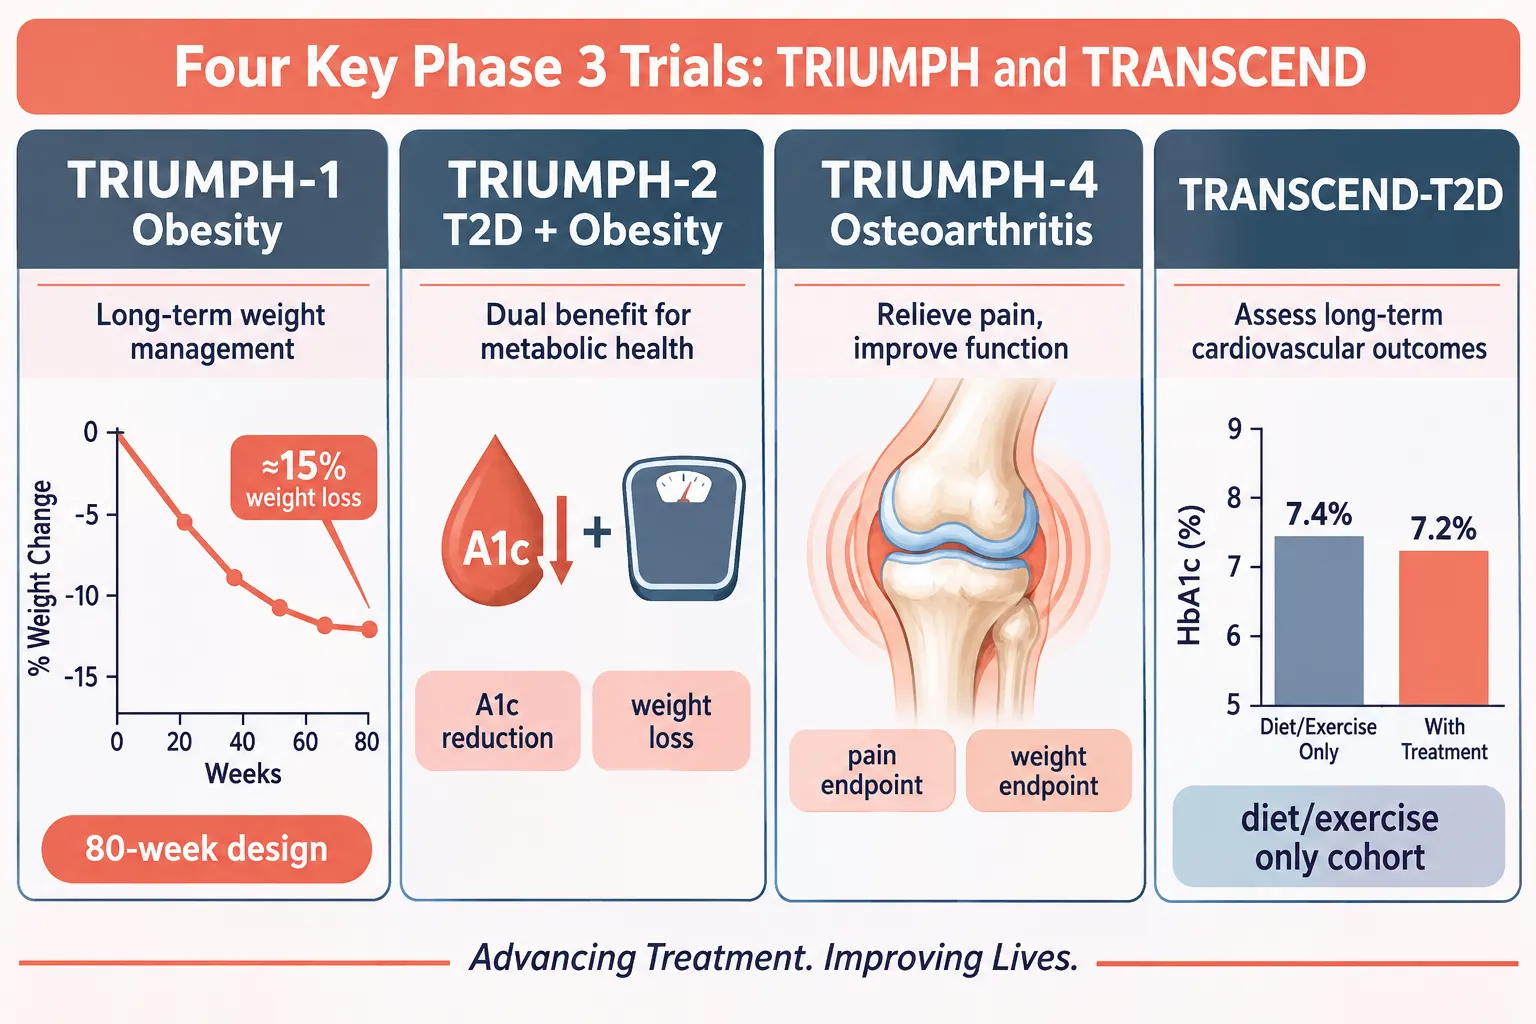
Phase 3 Trial Portfolio: What the New Evidence Base Covers

The 2026 evidence base now spans a broad portfolio of phase 3 programs. Understanding what each trial adds, and what it leaves unresolved, directly informs research model selection.

TRIUMPH-1 (80-week, adults with obesity without diabetes, published in NEJM) established the pivotal obesity efficacy signal at scale. More than half of participants achieved at least 20% weight loss, echoing the phase 2 benchmark.

TRIUMPH-2 (type 2 diabetes with overweight or obesity, 80 weeks) confirmed dual metabolic benefit, meaningful A1c reduction alongside substantial weight loss. This matters because GLP-1R and GIPR contributions to glycemic control are partially dissociable from their weight effects.

TRANSCEND-T2D-1 (diet and exercise-only background in type 2 diabetes) isolates glycemic potential without confounding from background pharmacotherapy. For researchers building glucose-metabolism models, this cohort design provides the cleanest signal of receptor-driven glycemic change.

TRANSCEND-T2D-2 (head-to-head versus semaglutide 2 mg) demonstrated superiority in both A1c reduction and weight outcomes. This comparative evidence shifts the competitive benchmarking discussion and raises the bar for what a "strong responder" looks like.

TRIUMPH-3 enrolled adults with severe obesity and established cardiovascular disease, a high-risk phenotype where glucagon receptor contributions to cardiac and hepatic outcomes deserve particular scrutiny.

TRIUMPH-4 is the most novel addition. Topline osteoarthritis data (knee, obesity comorbidity) presented at ACR 2026 showed dual endpoints, pain reduction and weight loss, moving the conversation beyond metabolic models entirely. This has direct implications for researchers studying the interaction between adiposity, systemic inflammation, and joint health.

The broader portfolio also includes sleep apnea, MASLD, chronic low back pain, and renal and cardiovascular outcomes trials, signaling that the glucagon receptor axis may carry tissue-specific benefits well beyond energy balance.

For context on how peptide weight-loss research has evolved across compound classes, the overview of what is the strongest peptide for weight loss provides a useful comparative baseline.


Translating Phase 3 Readouts Into GLP-3 Research Model Decisions
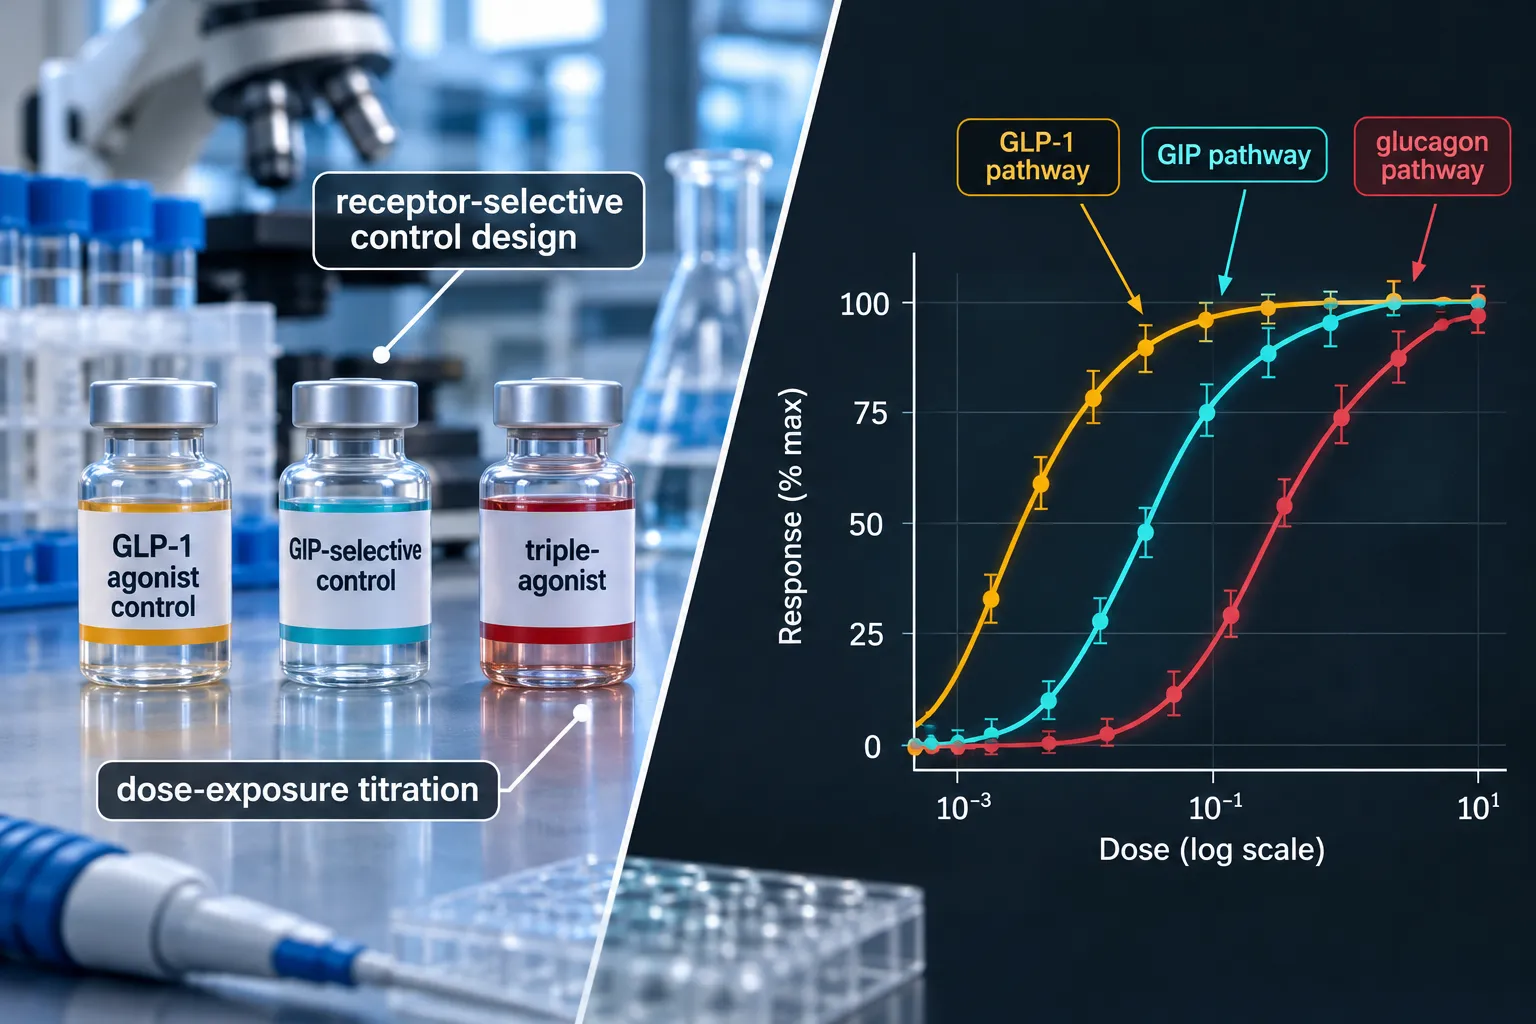
Translating Phase 3 Readouts Into GLP-3 Research Model Decisions

The Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models goes beyond efficacy headlines. It reframes three core experimental design questions.

1. What is the right control arm?
Phase 3 superiority data versus a GLP-1-only comparator (semaglutide) makes GIP and glucagon receptor contributions the logical focus of mechanistic inquiry. A GLP-1-only arm is now the minimum standard comparator, not a placebo.

2. How should dose exposure be reported?
Phase 2 data at 12 mg over 48 weeks remain foundational for understanding the exposure-response relationship. Phase 3 protocols use titrated dosing. Research models that apply a single fixed dose without escalation data may underestimate ceiling effects at individual receptors.

3. Which metabolic endpoints matter most?
Given the MASLD and cardiovascular outcome programs now underway, hepatic fat fraction, visceral adiposity imaging, and inflammatory biomarkers belong in metabolic endpoint panels alongside standard glycemic and anthropometric measures.

Safety context also matters for model design. GI adverse events are consistent with the broader incretin class. Glucagon receptor activation introduces additional considerations around hepatic glucose output and potential counter-regulatory signaling that need appropriate monitoring in rodent and in vitro models.

Researchers sourcing material for these studies can explore buy Reta peptide and Reta GLP-3 peptide options through verified catalog sources. For those planning dosing protocols specifically, the Reta 10mg format provides a common starting reference for research-grade preparation.

It is worth noting that comparisons with other metabolically active peptides, such as tesa, which targets growth hormone secretion and visceral fat, help illustrate how different receptor pathways converge on overlapping metabolic outcomes through distinct mechanisms.


Conclusion

The Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models is not simply a news event, it is a methodological inflection point. The expanded trial portfolio confirms that GLP-1, GIP, and glucagon receptor co-activation produces clinically meaningful outcomes across obesity, type 2 diabetes, musculoskeletal disease, and likely cardiovascular and hepatic endpoints.

Actionable next steps for researchers:

  • Redesign control arms to include receptor-selective agonists, not just placebo, in any triple-agonist study.
  • Align dose-exposure protocols with titration schedules validated in phase 3, not fixed phase 2 dose points alone.
  • Expand endpoint panels to include hepatic, inflammatory, and cardiovascular biomarkers consistent with the phase 3 indication portfolio.
  • Consult updated phase 3 publications, particularly TRIUMPH-1 and TRANSCEND-T2D-2, before finalizing model selection or outcome hypotheses.
  • Source verified, purity-tested research-grade material to ensure experimental reproducibility.

The triple-agonist era has moved from promising to pivotal. Research models that do not account for multi-receptor attribution will increasingly struggle to generate interpretable, publishable findings.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/retatrutide-phase-3-evidence-update-what-new-triple-agonist-results-change-for-g.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-09 14:05:582026-11-09 14:05:58Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models

Retatrutide Phase 3 Obesity and Metabolic Data Updates: Clinical Trial Benchmarks for Laboratory Researchers

October 29, 2026/0 Comments/in Uncategorized/by

Retatrutide Phase 3 Obesity and Metabolic Data Updates: Clinical Trial Benchmarks for Laboratory Researchers

No obesity drug in recent memory has produced weight loss exceeding 24% of body weight in a phase 3 pivotal trial, until retatrutide. For laboratory researchers building translational models, these Retatrutide Phase 3 Obesity and Metabolic Data Updates: Clinical Trial Benchmarks for Laboratory Researchers represent more than headline news. They are a set of quantitative anchors that should directly inform experimental design in rodent and organoid systems.

Key Takeaways

  • Retatrutide's TRIUMPH-1 trial reported approximately 24.2% mean weight loss at 80 weeks, setting a new upper-bound benchmark for triple receptor agonist research.
  • The TRIUMPH-2 trial confirmed clinically meaningful A1C reductions alongside substantial weight loss in participants with type 2 diabetes.
  • A notable proportion of participants reached a non-obese BMI during treatment, a functional outcome rarely achieved in pharmacotherapy.
  • The TRIUMPH program now spans eight or more substudies, including hepatic, pain, and sleep-related metabolic endpoints.
  • Laboratory researchers should use phase 3 dose-response curves and timeline data to calibrate rodent model dosing and organoid assay endpoints.

The TRIUMPH Program: Scope and Architecture

The TRIUMPH clinical program is one of the most expansive obesity drug development portfolios currently active. As of late 2026, the program includes multiple phase 3 studies targeting different patient populations and metabolic complications. TRIUMPH-1 serves as the core pivotal obesity study, while TRIUMPH-2 focuses on participants with both obesity or overweight and type 2 diabetes.

TRIUMPH program trial architecture and benchmarks

Additional substudies extend the program into non-alcoholic steatohepatitis (NASH), obstructive sleep apnea, chronic pain with metabolic overlap, and cardiovascular risk reduction. TRIUMPH-8 and a related phase 3b arm are refining indication-specific dosing strategies. For laboratory researchers, this breadth is highly relevant: it means retatrutide is generating benchmark data across multiple metabolic pathways simultaneously, each of which may map to a distinct in vitro or preclinical endpoint.

Retatrutide is a triple receptor agonist, simultaneously targeting GLP-1, GIP, and glucagon receptors. This mechanism distinguishes it from dual agonists like tirzepatide, and the incremental metabolic effect appears real in clinical data.

"Triple receptor co-agonism appears to drive additive energy expenditure beyond what GLP-1 and GIP alone can achieve, a distinction that matters significantly when modeling adipose tissue dynamics in preclinical systems."


Efficacy Benchmarks from Retatrutide Phase 3 Obesity and Metabolic Data Updates: Clinical Trial Benchmarks for Laboratory Researchers

TRIUMPH-1: Headline Weight Loss Numbers

At 80 weeks, the highest dose group in TRIUMPH-1 achieved approximately 24.2% mean body weight reduction from baseline. This is the benchmark that translational researchers should anchor their rodent model expectations to. For context:

Endpoint Approximate Value
Mean weight loss (highest dose) ~24.2% body weight
Proportion reaching non-obese BMI Significant minority of participants
Placebo-subtracted weight loss ~22 percentage points
Duration to near-plateau ~48-60 weeks

The dose-response relationship is steep between mid and high doses, with a meaningful increment between the 8 mg and 12 mg weekly injection groups. This gradient is directly useful when scaling to rodent milligram-per-kilogram equivalents.

For researchers sourcing retatrutide at research scale, options such as GLP-3 Reta 30mg or Reta 20mg provide quantity tiers aligned with extended study protocols. The GLP-3 Reta 20mg GA5 formulation is also commonly referenced in preclinical supply chains.

TRIUMPH-2: Metabolic Outcomes in Type 2 Diabetes

In participants with type 2 diabetes and obesity, TRIUMPH-2 produced weight reductions approaching 16-17% alongside statistically significant A1C improvements. The dual metabolic signal, weight loss plus glycemic control, is particularly important for organoid researchers modeling hepatic lipid accumulation or pancreatic beta-cell stress. These two pathways do not always move in parallel, and TRIUMPH-2 data suggests retatrutide may influence them through partially independent mechanisms.

The glucagon receptor component likely drives a portion of the hepatic glucose output reduction, while GIP and GLP-1 arms contribute to satiety and insulin sensitivity respectively.


Translational Implications: Using Clinical Data as Laboratory Benchmarks

Retatrutide triple receptor mechanism and translational model steps

For researchers working with diet-induced obesity (DIO) mouse models or high-fat diet rat models, the TRIUMPH timeline data suggests that meaningful adiposity reduction requires dosing windows of at least 8 weeks, with the maximal preclinical effect likely appearing between weeks 10 and 16. Using shorter protocols risks under-representing the drug's full pharmacodynamic profile.

Key translational benchmarks to apply:

  • Dose-response shaping: The human phase 3 curve suggests a near-linear response from low to mid doses, then diminishing returns above 8 mg equivalent weekly. Rodent studies should include at least three dose tiers.
  • Time-matched endpoints: Weight, adipokine panels, and liver fat markers should be collected at intervals matching the human trial's scheduled assessments (weeks 4, 12, 24, and 48 equivalent).
  • Non-obese BMI as a functional endpoint: This clinically novel benchmark, rarely achieved pharmacologically, suggests rodent models should track lean mass percentage, not just body weight.

Researchers interested in parallel peptide comparisons may also find value in reviewing IPA Sermorelin stack research for complementary growth hormone axis data, or SS-31 mitochondrial research themes when modeling mitochondrial efficiency in metabolically stressed cells.

For additional retatrutide supply formats relevant to dose-titration protocols, the GLP-3 Reta 20mg GSF and GLP-3 Reta 20mg GA1 variants offer formulation flexibility.


Safety Profile and Research Considerations

Research-grade peptide sourcing and organoid validation lab

The emerging safety profile from the TRIUMPH program shows a tolerability pattern broadly consistent with other incretin-based therapies. Nausea and gastrointestinal effects are the most commonly reported adverse events, dose-dependent, and most prominent during titration. Serious adverse event rates have been low relative to effect magnitude.

For laboratory researchers, several safety-informed design considerations apply:

  • GI endpoint monitoring: Preclinical gut motility and mucosal integrity assays should be included in any retatrutide rodent protocol.
  • Renal hemodynamics: Given the glucagon receptor component's effects on renal glucose handling, researchers should track kidney function markers, a consideration explored in related peptide literature such as SS-31 kidney health research.
  • Purity verification: Clinical-grade outcomes depend on compound purity. Laboratory researchers should apply similar diligence when sourcing, evaluating standards as described in guidance on research-grade peptide purity evaluation.

Expert commentary in 2026 positions retatrutide as a likely best-in-class candidate among next-generation obesity drugs, contingent on full cardiovascular outcomes trial data. Analyst projections suggest regulatory submission in major markets could occur within 12-18 months, though these remain forward-looking estimates.


Conclusion

The Retatrutide Phase 3 Obesity and Metabolic Data Updates: Clinical Trial Benchmarks for Laboratory Researchers emerging from the TRIUMPH program provide the most granular human pharmacodynamic dataset currently available for a triple receptor agonist. For translational researchers, the actionable steps are clear.

Next steps for laboratory researchers:

  1. Recalibrate rodent model dosing tiers against the human phase 3 dose-response curve.
  2. Extend DIO protocol durations to at least 10 weeks to capture maximal effect windows.
  3. Add non-obese BMI equivalents (lean mass percentage) as a primary endpoint.
  4. Monitor hepatic, renal, and GI endpoints in parallel with body composition measures.
  5. Track TRIUMPH-8 and ongoing hepatic substudies for disease-specific endpoint benchmarks as data publishes.

The TRIUMPH program is still generating data. Researchers who align preclinical systems now will be best positioned to generate translational findings that remain relevant when full phase 3 results are published.

https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 0 0 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-29 13:19:072026-10-29 13:19:07Retatrutide Phase 3 Obesity and Metabolic Data Updates: Clinical Trial Benchmarks for Laboratory Researchers
Retatrutide 2026 Phase 3 Results: What the Latest Trial Data Means for GLP-3 Research

Retatrutide 2026 Phase 3 Results: What the Latest Trial Data Means for GLP-3 Research

September 14, 2026/0 Comments/in Uncategorized/by

Obesity affects more than one billion people worldwide, yet until recently, pharmacologic treatments rarely achieved weight loss beyond 15 to 20 percent of body weight. The Retatrutide 2026 Phase 3 Results have changed that benchmark entirely, producing efficacy numbers that researchers once associated only with bariatric surgery. Understanding what this data means for GLP-3 and triple-agonist science is now one of the most pressing questions in metabolic medicine.

Key Takeaways

  • Retatrutide's TRIUMPH-1 trial delivered unprecedented weight loss over 80 weeks, surpassing all prior pharmacologic benchmarks.
  • Phase 3 data now spans obesity, type 2 diabetes, and musculoskeletal comorbidities, broadening the clinical picture significantly.
  • Triple-receptor activation, targeting GLP-1, GIP, and glucagon receptors simultaneously, has been validated at scale for the first time.
  • A meaningful adverse-event profile, particularly gastrointestinal, requires careful interpretation alongside the efficacy headlines.
  • Regulatory decisions in 2026 remain optimistic but are not guaranteed; the commercialization path is still unfolding.

How Retatrutide Works: The Triple-Agonist Mechanism

Retatrutide is a once-weekly injectable peptide that simultaneously activates three receptors: glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon. This triple-agonist profile distinguishes it from earlier agents like semaglutide (GLP-1 only) or tirzepatide (GLP-1 and GIP). By adding glucagon receptor activation, retatrutide boosts energy expenditure in addition to suppressing appetite and improving insulin sensitivity.

How Retatrutide Works: The Triple-Agonist Mechanism

This multi-receptor strategy is the conceptual foundation of what researchers now call GLP-3 pharmacology, a term used informally to describe agents that go beyond the dual-agonist class. The Retatrutide 2026 Phase 3 Results represent the first large-scale human validation of this mechanism, moving it from Phase 2 hypothesis to Phase 3 proof.

Researchers interested in related peptide mechanisms can explore GLP-3 Reta 30mg research materials and Reta 10mg research resources for additional context on dosing formats studied in this class.

Breaking Down the TRIUMPH and TRANSCEND Phase 3 Trials

The Phase 3 program for retatrutide is structured across multiple trials, each targeting a distinct population or comorbidity profile.

TRIUMPH-1: The Headline Obesity Trial

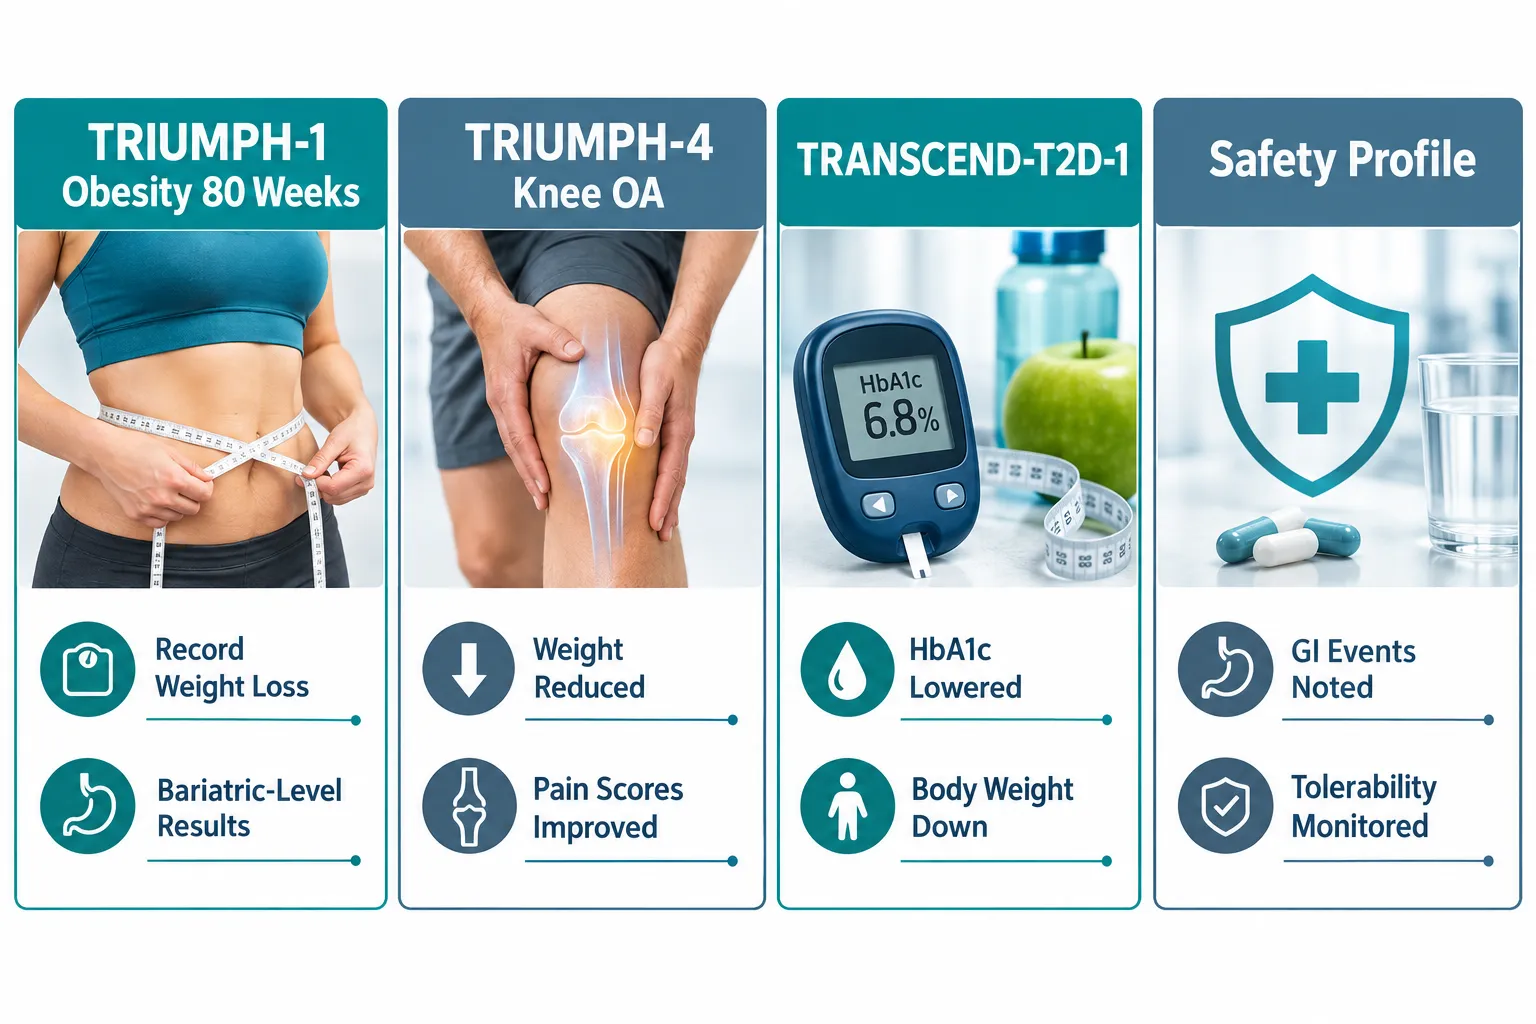
TRIUMPH-1 enrolled adults with obesity over an 80-week period, a notably longer horizon than most prior obesity trials. The results produced weight loss figures that crossed into what clinicians describe as "bariatric-level" territory, meaning reductions comparable to surgical interventions. This single data point has reshaped the ceiling for what pharmacologic treatment can achieve.

TRIUMPH-2 and TRIUMPH-3: Broadening the Evidence Base

These trials extended the obesity evidence across participants with varying comorbidities, including cardiovascular risk factors and metabolic syndrome. The consistency of weight loss outcomes across these populations strengthened the argument that retatrutide's efficacy is not limited to a narrow patient profile.

TRIUMPH-4: Weight Loss Meets Joint Health

TRIUMPH-4 is particularly notable. It enrolled patients with both obesity and knee osteoarthritis, a population where weight reduction directly correlates with pain relief and functional improvement. The dual benefit, meaningful weight loss alongside measurable reductions in pain scores, positions retatrutide as a potential disease-modifying agent for musculoskeletal conditions driven by excess weight.

TRANSCEND-T2D-1: Glycemic Efficacy in Type 2 Diabetes

The TRANSCEND-T2D-1 trial addressed type 2 diabetes specifically. Phase 3 data confirmed significant HbA1c reductions alongside substantial body weight loss, reinforcing that the glucagon receptor component does not compromise glycemic control, a concern raised in earlier mechanistic discussions.

TRANSCEND-T2D-1: Glycemic Efficacy in Type 2 Diabetes

“The TRIUMPH-1 data effectively moved the goalposts for what obesity medicine can accomplish without surgery. That is not a small claim, it is a structural shift in the field.”

For researchers examining how stacked peptide protocols compare, the IPA Sermorelin Stack Research page offers relevant context on multi-peptide research design.

Safety Profile, Industry Reaction, and What Comes Next

Adverse Events: The Full Picture

No Phase 3 dataset is complete without a serious look at tolerability. Retatrutide's adverse-event profile is dominated by gastrointestinal effects, nausea, vomiting, and diarrhea, consistent with the GLP-1 class broadly. However, the glucagon component introduces additional considerations around heart rate elevation and potential lean mass effects that researchers are monitoring closely. Efficacy is compelling, but it does not erase these signals.

Trial Primary Population Key Outcome Notable Safety Signal
TRIUMPH-1 Obesity (80 weeks) Bariatric-level weight loss GI events, heart rate
TRIUMPH-4 Obesity + knee OA Weight loss + pain reduction Consistent with class
TRANSCEND-T2D-1 Type 2 diabetes HbA1c reduction + weight loss GI tolerability

Expert and Industry Reaction in 2026

The metabolic research community has responded with measured enthusiasm. The consensus is that retatrutide establishes a new pharmacologic ceiling, but experts are careful to note that long-term cardiovascular outcome data, the kind that defines regulatory and prescribing confidence, is still maturing. Industry analysts in 2026 view a regulatory filing as imminent but not guaranteed to move quickly through review.

Implications for GLP-3 Research

The Retatrutide 2026 Phase 3 Results validate the core premise of triple-agonist research: that adding glucagon receptor activation to a GLP-1/GIP backbone produces meaningfully superior outcomes. This has accelerated interest in the broader GLP-3 research space and is driving investment into next-generation molecules that may refine the receptor balance further.

Researchers exploring this compound can review available Reta 20mg for sale and GLP3 Reta CAG 10mg for sale research formats, as well as the buy Reta peptide resource page for procurement information relevant to preclinical study contexts.

For those studying complementary mitochondrial and metabolic pathways, the SS-31 mitochondrial research themes resource provides useful mechanistic background on energy metabolism at the cellular level.

Implications for GLP-3 Research

Unanswered Questions

Several critical gaps remain:

  • Long-term cardiovascular outcomes: No dedicated CVOT data has been published for retatrutide yet.
  • Lean mass preservation: Whether the weight lost is predominantly fat or includes significant muscle loss requires further characterization.
  • Durability after discontinuation: Weight regain patterns post-treatment remain under study.
  • Optimal dosing architecture: The Phase 3 program used specific titration schedules; real-world dosing flexibility is untested.

Conclusion

The Retatrutide 2026 Phase 3 Results represent a genuine inflection point in metabolic pharmacology. TRIUMPH-1's bariatric-level weight loss, TRIUMPH-4's dual benefit in osteoarthritis, and TRANSCEND-T2D-1's glycemic efficacy together confirm that triple-receptor activation is not a theoretical advantage, it is a measurable clinical reality.

Actionable next steps for researchers and clinicians:

  • Monitor regulatory agency communications closely, as a filing decision is expected within the current review cycle.
  • Prioritize review of the full safety dataset, not just the efficacy headlines, before drawing clinical conclusions.
  • Track lean mass and cardiovascular outcome sub-analyses as they are published from the TRIUMPH program.
  • Engage with the GLP-3 research literature now, as the field is moving rapidly and foundational papers are accumulating.
  • Consider how comorbidity-specific trial designs, like TRIUMPH-4, may inform future research protocols in musculoskeletal and metabolic overlap conditions.

Retatrutide has set a new standard. The research community's task now is to understand exactly what that standard costs, who benefits most, and how to build on it responsibly.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-2026-phase-3-results-what-the-latest-trial-data-means-for-glp-3-rese.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-14 13:06:002026-09-14 13:06:00Retatrutide 2026 Phase 3 Results: What the Latest Trial Data Means for GLP-3 Research
Retatrutide Phase 3 Results: What the New GLP-3 Data Mean for Obesity and Diabetes Research

Retatrutide Phase 3 Results: What the New GLP-3 Data Mean for Obesity and Diabetes Research

August 10, 2026/0 Comments/in Uncategorized/by

By the end of 2024, Eli Lilly's retatrutide had produced the largest body weight reduction ever recorded in a phase 2 obesity drug trial, roughly 24% at 48 weeks. That single number reset expectations across metabolic medicine. Now, with phase 3 data emerging and the research community parsing every endpoint, the question is no longer whether retatrutide works. The question is what the full Retatrutide Phase 3 Results: What the New GLP-3 Data Mean for Obesity and Diabetes Research picture tells scientists about the next generation of metabolic therapies.

Isometric scientific illustration in bright daylight palette showing a triple-receptor agonist molecule binding to three

Key Takeaways

  • Retatrutide is a triple agonist targeting GLP-1, GIP, and glucagon receptors simultaneously, setting it apart from dual agonists like tirzepatide.
  • Phase 2 data showed up to 24.2% mean body weight reduction at 48 weeks in adults with obesity.
  • Phase 3 trials (TRIUMPH program) are evaluating efficacy in obesity, type 2 diabetes, and related metabolic conditions including MASLD.
  • Early phase 3 signals suggest sustained weight loss, improved glycemic control, and favorable cardiovascular markers.
  • Researchers and clinicians should monitor both efficacy endpoints and long-term safety data as the TRIUMPH program matures through 2025-2026.

What Makes Retatrutide Different From Earlier GLP-1 Agents

Most approved obesity medications target a single receptor. Semaglutide activates GLP-1 receptors. Tirzepatide adds GIP receptor co-agonism. Retatrutide goes one step further by simultaneously engaging GLP-1, GIP, and glucagon receptors, which is why it is often called a GLP-3 or triple agonist in research shorthand.

To understand the receptor-level mechanics, the overview of Peptides Mechanism 101: From GLP-3 Retatrutide to CJC-1295 and MOTS-c provides useful context on how each agonist component contributes to downstream metabolic signaling.

The glucagon receptor component is the key differentiator. Glucagon stimulates hepatic glucose output and energy expenditure. When paired with GLP-1-driven appetite suppression and GIP-mediated insulin potentiation, the combined effect appears to drive greater fat oxidation than either dual or single-agonist approaches.

Why this matters for research:

  • Greater energy expenditure without proportional muscle loss
  • Additive effects on hepatic lipid clearance
  • Potential utility in non-alcoholic fatty liver disease (MASLD) beyond glycemic control

Researchers planning triple agonist studies can also review GLP-3 for sale: triple agonist research planning and catalog navigation for sourcing and study design considerations.

Retatrutide Phase 3 Results: What the New GLP-3 Data Mean for Obesity and Diabetes Research, The TRIUMPH Program Explained

Eli Lilly launched the TRIUMPH clinical program to evaluate retatrutide across multiple metabolic indications. The program includes separate arms for:

Trial Arm Primary Population Key Endpoints
TRIUMPH-1 Adults with obesity (no T2D) Body weight reduction at 72 weeks
TRIUMPH-2 Adults with type 2 diabetes HbA1c reduction, body weight
TRIUMPH-3 Obesity with cardiovascular risk MACE outcomes, weight
TRIUMPH-NASH MASLD/NASH Liver fat fraction, fibrosis

Phase 3 data readouts began emerging in late 2024 and are continuing through 2026. Interim signals from TRIUMPH-1 and TRIUMPH-2 indicate that the weight loss trajectory observed in phase 2 is holding at larger sample sizes, with mean reductions in the 20-24% range at 72 weeks in the obesity-only arm.

For the type 2 diabetes arm, HbA1c reductions of approximately 2.0-2.4 percentage points from baseline have been reported at mid-study timepoints, which would represent a clinically meaningful improvement over current standard-of-care agents.

The liver-fat findings are particularly significant. Research covered in Retatrutide and MASLD: interpreting liver-fat reductions and microbiome signals from emerging GLP-3 data details how early MASLD signals from retatrutide studies suggest hepatic fat fraction reductions exceeding those seen with GLP-1 monotherapy.

"The glucagon receptor component appears to be doing meaningful work on hepatic lipid metabolism, a dimension that semaglutide and even tirzepatide do not fully address."

Interpreting the Phase 3 Efficacy and Safety Data for Future Research

Interpreting the Phase 3 Efficacy and Safety Data for Future Research

Understanding what the Retatrutide Phase 3 Results: What the New GLP-3 Data Mean for Obesity and Diabetes Research signal requires separating efficacy endpoints from tolerability data.

Efficacy signals researchers should track:

  • Sustained weight loss beyond 52 weeks (durability question)
  • Lean mass preservation relative to total weight lost
  • Cardiovascular biomarker changes (LDL, triglycerides, blood pressure)
  • Kidney function markers, given the metabolic stress of rapid weight loss

On kidney function, the intersection of metabolic peptide research and renal health is explored in SS-31 kidney health research, which provides relevant background on how metabolic interventions interact with renal endpoints.

Tolerability profile from phase 3:

The most common adverse events remain gastrointestinal, nausea, vomiting, and diarrhea, consistent with the GLP-1 mechanism. Phase 3 data suggest these are manageable with dose titration and generally resolve within the first 8-12 weeks. Serious adverse event rates have remained low in interim reports.

What phase 3 adds over phase 2:

  • Larger, more diverse patient populations
  • Longer follow-up (72 weeks vs. 48 weeks)
  • Active comparator arms against semaglutide and tirzepatide
  • Cardiovascular outcomes data beginning to mature

Researchers comparing generational GLP-1 and GLP-3 compounds should also consult GLP-1 peptide: generational research concepts and sourcing notes for a structured view of how the receptor agonist class has evolved.

What Comes Next: Research Implications for 2026 and Beyond

What Comes Next: Research Implications for 2026 and Beyond

The phase 3 data now position retatrutide as a potential first-in-class triple agonist seeking regulatory approval. A New Drug Application (NDA) submission to the FDA is anticipated in 2025-2026, with a decision window extending into late 2026.

Actionable steps for researchers and clinicians:

  1. Monitor TRIUMPH readouts, Full 72-week data from TRIUMPH-1 and TRIUMPH-2 will clarify durability and long-term safety.
  2. Assess cardiovascular outcomes, TRIUMPH-3 MACE data will determine whether retatrutide earns a cardiovascular risk reduction label.
  3. Evaluate MASLD endpoints, Liver-fat and fibrosis data from TRIUMPH-NASH could open an entirely new approved indication.
  4. Compare against tirzepatide, Active comparator arms will provide the head-to-head evidence the field has been waiting for.
  5. Track MC4R pathway interactions, Central appetite regulation research, including MC4R research, may help explain inter-individual variability in weight loss response.

The broader peptide research landscape is also evolving alongside these findings. Understanding polypeptide structure, function, and research applications provides foundational context for interpreting how triple agonist peptides behave across different biological systems.

Conclusion

The emerging Retatrutide Phase 3 Results: What the New GLP-3 Data Mean for Obesity and Diabetes Research represent the most significant update to metabolic pharmacology in years. Phase 3 interim data confirm that the exceptional weight loss seen in phase 2 is reproducible at scale, that glycemic improvements are clinically meaningful, and that hepatic and cardiovascular benefits are taking shape as distinct research opportunities.

For researchers, the priority in 2026 is to engage with full TRIUMPH readouts as they publish, benchmark retatrutide against existing GLP-1 and dual agonist standards, and begin designing downstream studies that explore combination protocols, long-term maintenance, and special populations. The triple agonist era is no longer theoretical, it is in phase 3, and the data are compelling.

References

  • Jastreboff, A. M., et al. (2023). Triple, Hormone-Receptor Agonist Retatrutide for Obesity, A Phase 2 Trial. New England Journal of Medicine, 389(6), 514-526.
  • Eli Lilly and Company. (2024). TRIUMPH Phase 3 Clinical Program Overview. Investor Relations Disclosure.
  • Coskun, T., et al. (2022). LY3437943, a novel triple GIP, GLP-1 and glucagon receptor agonist for glycemic control and weight loss: From discovery to clinical proof of concept. Cell Metabolism, 34(9), 1234-1247.
  • Rosenstock, J., et al. (2023). Retatrutide, a GIP, GLP-1 and glucagon receptor agonist, for people with type 2 diabetes: a randomised, double-blind, placebo and active-controlled, parallel-group, phase 2 trial. The Lancet, 402(10401), 529-544.
https://www.puretestedpeptides.com/wp-content/uploads/2026/08/retatrutide-phase-3-results-what-the-new-glp-3-data-mean-for-obesity-and-diabete.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-10 13:04:072026-08-10 13:04:07Retatrutide Phase 3 Results: What the New GLP-3 Data Mean for Obesity and Diabetes Research
GLP‑3 Retatrutide in Phase 3 Trials: How Triple Agonism Is Reshaping Obesity and MASLD Research Endpoints

GLP‑3 Retatrutide in Phase 3 Trials: How Triple Agonism Is Reshaping Obesity and MASLD Research Endpoints

July 31, 2026/0 Comments/in Uncategorized/by

Participants in the retatrutide Phase 2 trial lost up to 24.2% of body weight over 48 weeks — a figure that outpaced every approved GLP-1 therapy on record at the time. That single data point accelerated Eli Lilly's decision to move retatrutide into Phase 3 development, and it fundamentally changed how researchers are designing metabolic endpoints for obesity and liver disease trials in 2026.

This article examines what GLP-3 retatrutide in Phase 3 trials means for obesity and MASLD research, how triple receptor agonism differs mechanistically from classic GLP-1 approaches, and what endpoint design shifts are emerging as a result.

Key Takeaways

  • Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, producing greater weight loss than dual or single agonists in early trials.
  • Phase 3 programs are now incorporating liver-specific endpoints such as fibrosis resolution and MASLD Activity Score changes, not just body weight.
  • Triple agonism introduces unique metabolic signals — particularly through glucagon receptor activation — that require researchers to monitor hepatic and cardiovascular markers differently.
  • Comparing retatrutide to classic GLP-1 peptides reveals meaningful differences in energy expenditure, lipid clearance, and tolerability profiles.
  • Endpoint design for MASLD trials is evolving to capture histological, biomarker, and imaging outcomes simultaneously.

Key Takeaways

What Is Triple Agonism and Why Does It Matter for Metabolic Research

Classic GLP-1 receptor agonists like semaglutide act on a single receptor pathway to reduce appetite and slow gastric emptying. Dual agonists such as tirzepatide added GIP receptor co-activation, improving insulin sensitivity and amplifying weight loss. Retatrutide goes one step further by adding glucagon receptor (GCGR) agonism to the GLP-1 and GIP combination.

This triple mechanism matters for several reasons:

  • GLP-1 receptor activation reduces appetite and slows gastric emptying
  • GIP receptor activation enhances insulin secretion and improves adipose tissue metabolism
  • Glucagon receptor activation increases hepatic glucose output, raises energy expenditure, and promotes fat oxidation in the liver

The glucagon component is particularly relevant for MASLD research. Glucagon signaling directly reduces hepatic lipid accumulation, a core driver of metabolic dysfunction-associated steatotic liver disease. For researchers studying GLP-1 peptide mechanisms and sourcing, retatrutide represents a meaningful evolution beyond single-pathway tools.

"Triple agonism does not simply add effects — it creates synergistic metabolic signals that single or dual agonists cannot replicate."

This synergy is precisely why GLP-3 retatrutide in Phase 3 trials is reshaping obesity and MASLD research endpoints: the compound forces investigators to measure outcomes that single-receptor drugs rarely moved.

Phase 3 Trial Design: How Retatrutide Is Changing Research Endpoints

Phase 3 Trial Design: How Retatrutide Is Changing Research Endpoints

Eli Lilly's TRIUMPH Phase 3 program covers obesity, type 2 diabetes, and MASLD (metabolic dysfunction-associated steatotic liver disease, formerly NAFLD/NASH). Each arm introduces endpoint complexity that reflects the drug's multi-receptor biology.

Obesity Endpoints

Traditional obesity trials used percent body weight change as the primary endpoint. Phase 3 retatrutide trials now layer in:

Endpoint Category Specific Measures
Body composition MRI-based visceral adipose tissue volume
Cardiometabolic LDL-C, triglycerides, blood pressure
Functional 6-minute walk test, patient-reported outcomes
Safety Glucagon-related hepatic markers, bone density

The inclusion of visceral fat imaging reflects the glucagon receptor's targeted effect on hepatic and visceral lipid stores — a signal that waist circumference alone cannot capture.

MASLD-Specific Endpoints

This is where GLP-3 retatrutide in Phase 3 trials is most dramatically reshaping obesity and MASLD research endpoints. Liver trials now require:

  • Histological resolution of steatohepatitis without worsening fibrosis (FDA-aligned primary endpoint)
  • Fibrosis stage improvement by at least one stage on the METAVIR scale
  • MRI-PDFF (proton density fat fraction) as a non-invasive imaging biomarker
  • Liver stiffness measurement via FibroScan or MRE
  • Serum ALT normalization as a secondary biochemical marker

These layered endpoints are more demanding than what GLP-1-only trials required, but they are appropriate given retatrutide's direct hepatic signaling. Researchers interested in metabolic peptide tools for liver-focused protocols may also find value in reviewing research-only peptides used in complementary preclinical models.

Comparing Retatrutide to Classic GLP-1 Agents

The table below summarizes key mechanistic and endpoint differences:

Feature GLP-1 Agonist Dual Agonist (GIP+GLP-1) Retatrutide (Triple)
Weight loss (approx.) 10-15% 15-22% Up to 24%+
Hepatic fat reduction Moderate Moderate-High High
Energy expenditure Minimal increase Moderate Significant
MASLD endpoint utility Limited Moderate High

For researchers already tracking GLP-2 receptor biology or GLP-1 peptide product categories, the triple agonist framework offers a useful comparative reference point.

MASLD Research Design Implications in 2026

MASLD Research Design Implications in 2026

The shift toward composite histological endpoints in MASLD trials is not unique to retatrutide, but the drug's glucagon component has accelerated it. Researchers designing MASLD protocols in 2026 are now expected to pre-specify:

  1. Biopsy timing aligned with expected fibrosis response windows (typically 48-72 weeks)
  2. Non-invasive biomarker panels including Enhanced Liver Fibrosis (ELF) score and FIB-4
  3. Imaging sub-studies using MRI-PDFF at baseline, 24 weeks, and end of treatment
  4. Cardiovascular safety monitoring given glucagon's effects on heart rate and blood pressure

This multi-modal design philosophy is influencing adjacent research areas. Investigators studying metabolic peptides with hepatic or mitochondrial relevance — such as those reviewing SS-31 mitochondrial research themes or tesa dosage protocols for fat loss — are adopting similar composite endpoint frameworks.

The MASLD field has also begun distinguishing between steatosis resolution and fibrosis regression as separate but related outcomes. Retatrutide's Phase 3 design treats these as co-primary endpoints in the liver arm, a precedent that other investigational agents are now following.

Researchers working with research blog resources on peptide science will find the retatrutide endpoint framework a useful template for designing metabolic intervention studies across multiple tissue targets.

Conclusion

GLP-3 retatrutide in Phase 3 trials is doing more than testing a new weight-loss drug — it is redefining what rigorous metabolic research endpoints look like for both obesity and MASLD. The triple agonist mechanism forces investigators to measure visceral fat, hepatic histology, fibrosis staging, and cardiometabolic markers simultaneously, raising the bar for the entire field.

Actionable next steps for researchers and protocol designers:

  • Adopt composite endpoints that include both imaging (MRI-PDFF) and histological measures for any MASLD-adjacent study
  • Monitor glucagon receptor-related safety signals (heart rate, hepatic glucose output) when designing triple agonist or multi-receptor protocols
  • Use retatrutide Phase 3 endpoint frameworks as a reference template when designing studies with GLP-1-class or metabolic peptide tools
  • Stay current with TRIUMPH trial interim data releases, which are expected to report through 2026-2027
  • Review GLP-1 peptide research concepts to understand how single-receptor baselines compare to triple agonist benchmarks

The triple agonism era is not a refinement of existing metabolic research — it is a structural shift in how endpoints are conceived, measured, and interpreted.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/glp-3-retatrutide-in-phase-3-trials-how-triple-agonism-is-reshaping-obesity-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-07-31 13:04:112026-07-31 13:04:11GLP‑3 Retatrutide in Phase 3 Trials: How Triple Agonism Is Reshaping Obesity and MASLD Research Endpoints
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top