Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: serm pharmacology

Estrogen Receptor Pharmacology, Enclomiphene, and Polypeptide Hormones: A Researcher’s Guide to serm–Peptide Interface

Estrogen Receptor Pharmacology, Enclomiphene, and Polypeptide Hormones: A Researcher’s Guide to serm–Peptide Interface

September 5, 2026/0 Comments/in Uncategorized/by

Fewer than 15% of preclinical endocrine studies formally account for estrogen receptor subtype selectivity when co-administering peptide hormones, a gap that routinely distorts biomarker interpretation and undermines reproducibility. For researchers designing assays at the intersection of selective estrogen receptor modulation and polypeptide signaling, that oversight is costly. This guide to Estrogen Receptor Pharmacology, Enclomiphene, and Polypeptide Hormones: A Researcher's Guide to serm, Peptide Interface bridges that gap, walking through receptor biology, enclomiphene's mechanism, and the practical considerations that arise when serms and peptide hormones share the same experimental model.

Key Takeaways

  • Estrogen receptors ERα, ERβ, and GPER each produce distinct downstream signals that interact differently with polypeptide hormone pathways.
  • Enclomiphene, the trans-isomer of clomiphene, acts as a pure ER antagonist at the hypothalamic, pituitary level without the estrogenic residual activity of its zuclomiphene counterpart.
  • serm activity modulates the HPG axis in ways that directly alter LH, FSH, and downstream peptide hormone output, making receptor subtype mapping essential before assay design.
  • Next-generation ER-targeted agents, including SERDs, PROTACs, and CERANs, introduce new variables when combined with polypeptide research compounds.
  • Rigorous third-party peptide testing and validated biomarker panels are non-negotiable for reliable serm, peptide interface data.

Estrogen Receptor Basics: ERα, ERβ, and GPER
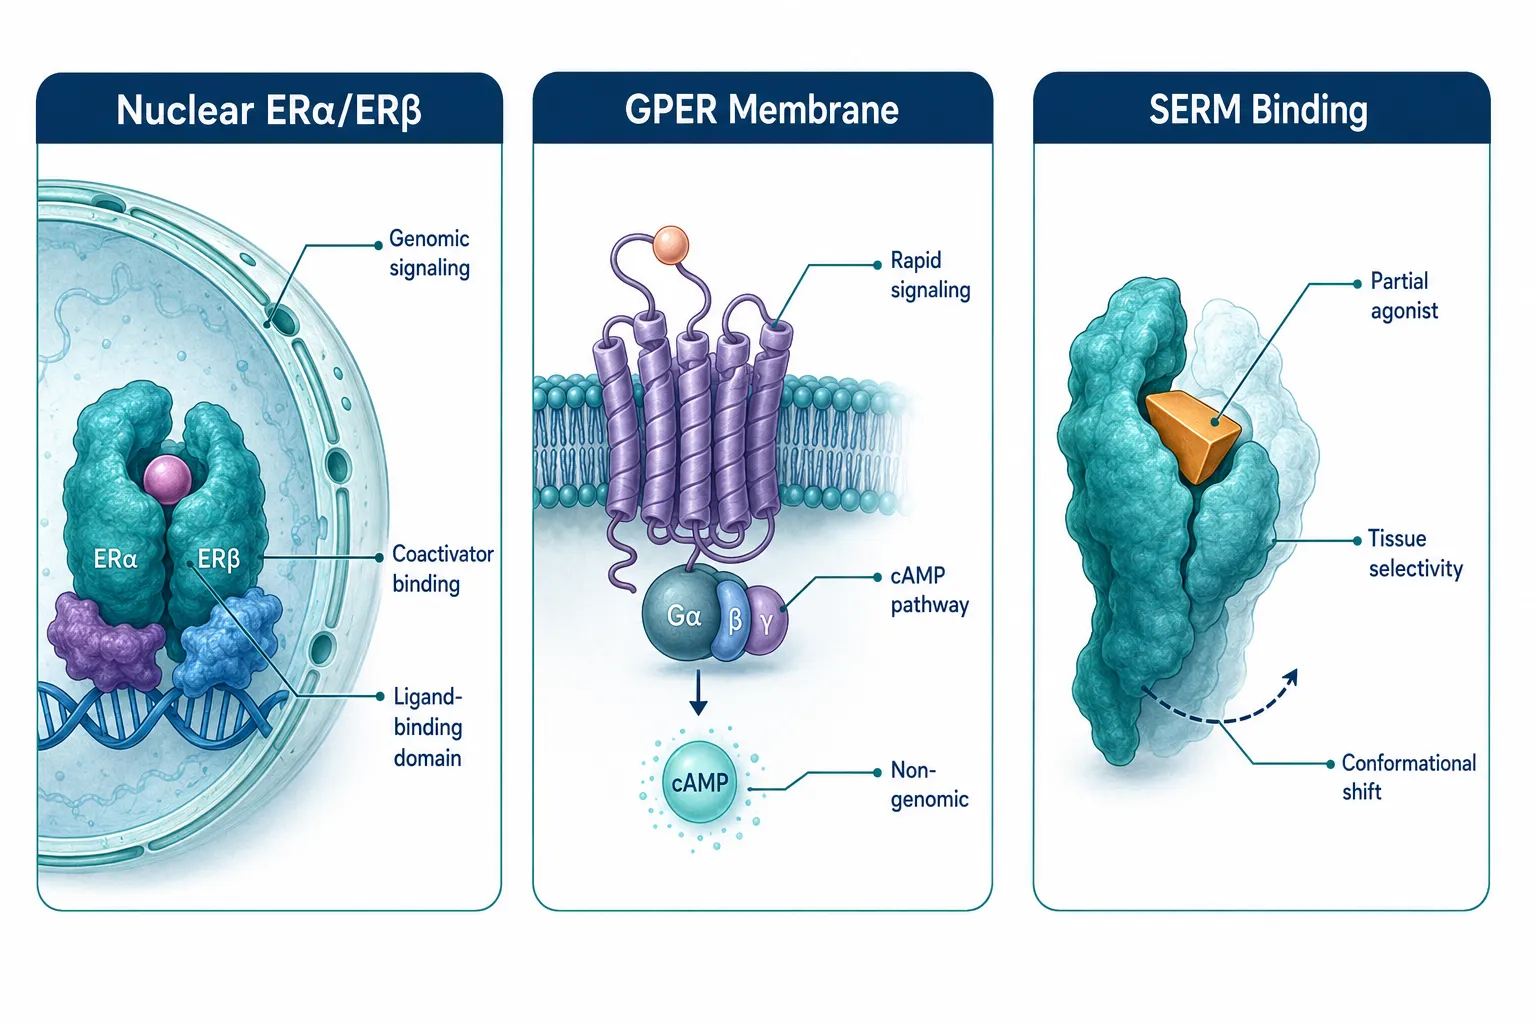
Estrogen Receptor Basics: ERα, ERβ, and GPER

Estrogen receptors are not a single target. Three pharmacologically distinct subtypes govern estrogen signaling across tissues:

Receptor Location Primary Signaling Mode Key Research Relevance
ERα Uterus, breast, liver, bone Genomic (nuclear) Proliferative responses, HPG feedback
ERβ Brain, ovary, vasculature Genomic + non-genomic Neuroprotection, anti-proliferative
GPER (GPR30) Membrane-bound, widespread Rapid non-genomic (cAMP) Fast estrogenic responses, peptide cross-talk

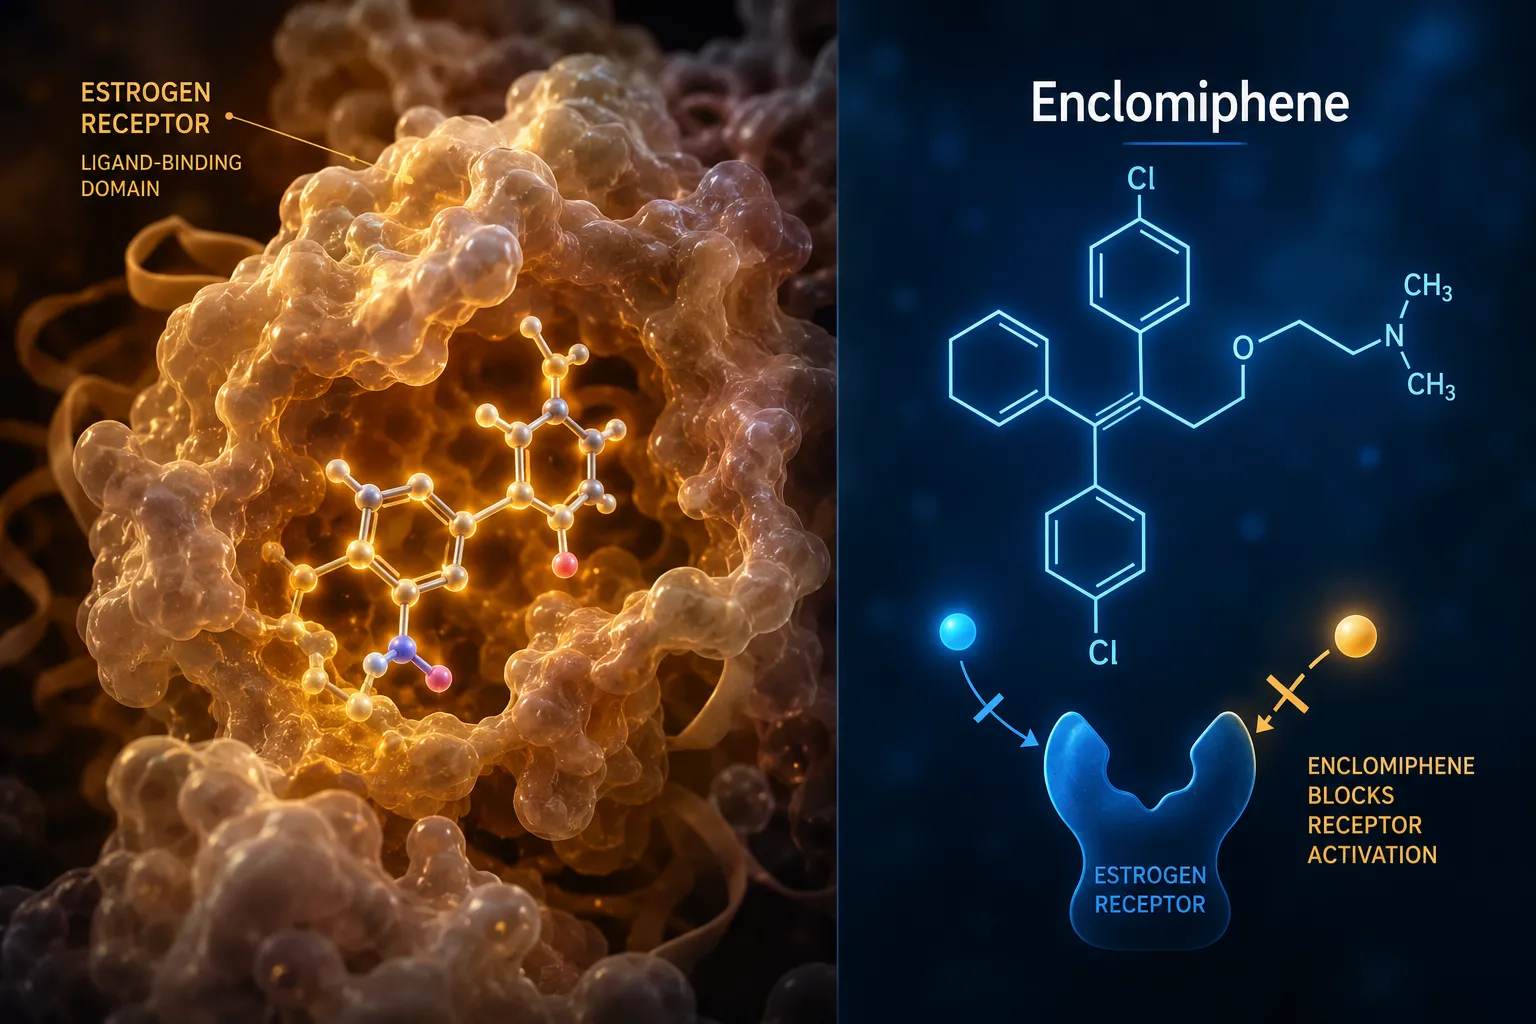
When a serm like enclomiphene binds ERα, it induces a conformational shift in the ligand-binding domain that prevents coactivator recruitment. The result is tissue-selective antagonism, blocking estrogenic negative feedback at the hypothalamus while potentially acting differently at other ERα-expressing sites. ERβ binding profiles vary widely across serm scaffolds, and GPER remains incompletely characterized for most clinical-stage serms as of 2026.

For researchers exploring selective estrogen receptor modulation, understanding which subtype dominates in the target tissue is the first design decision, not an afterthought.

Why this matters for peptide co-administration: Growth hormone (GH), GLP-class peptides, and gonadotropin-releasing hormone (GnRH) analogs all operate within tissues that co-express estrogen receptors. Signal cross-talk is not hypothetical; it is structural.

Enclomiphene Pharmacology and the HPG Axis
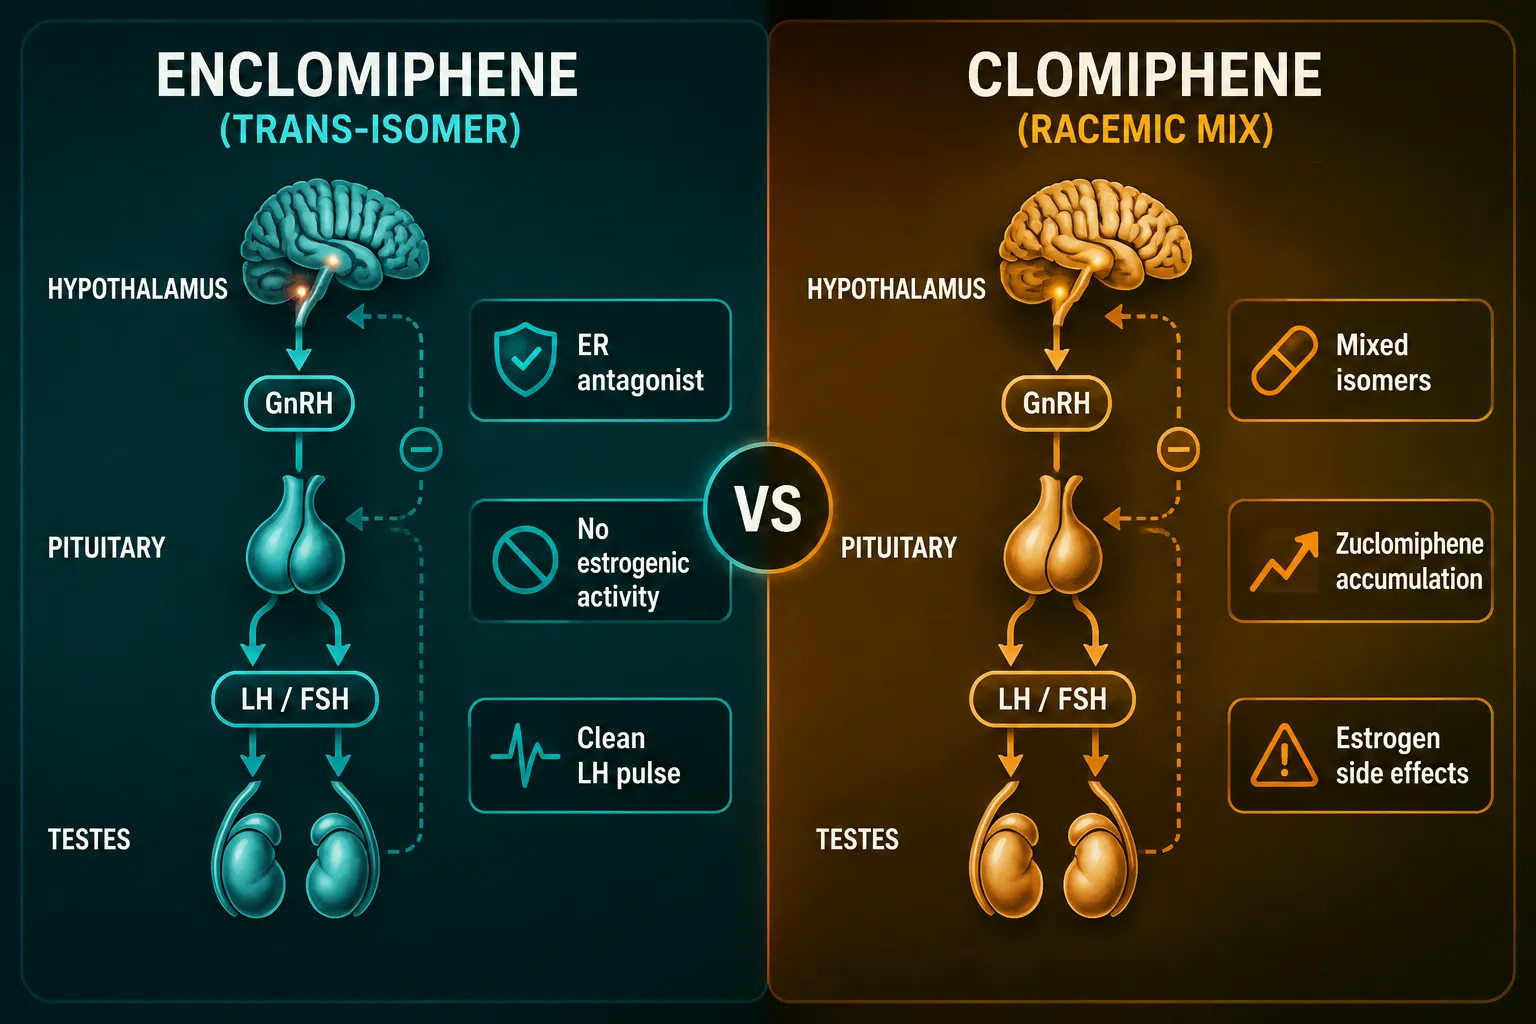
Enclomiphene Pharmacology and the HPG Axis

Clomiphene citrate is a racemic mixture of two geometric isomers: zuclomiphene (cis) and enclomiphene (trans). Their pharmacological profiles diverge sharply.

Enclomiphene (trans-isomer):

  • Half-life approximately 10 hours, clears rapidly
  • Pure ER antagonist at hypothalamic ERα
  • Blocks estrogen-mediated suppression of GnRH pulsatility
  • Elevates LH and FSH without residual estrogenic activity

Zuclomiphene (cis-isomer):

  • Half-life exceeding 30 days, accumulates with repeated dosing
  • Partial ER agonist activity
  • Responsible for most estrogen-related side effects attributed to clomiphene

"Isolating the trans-isomer eliminates the pharmacological noise introduced by zuclomiphene accumulation, producing a cleaner HPG axis stimulus for research models."

In male hypogonadism research, enclomiphene has demonstrated the ability to restore LH and testosterone levels while preserving spermatogenesis, an outcome that racemic clomiphene compromises through its estrogenic component. This distinction is central to serm pharmacology research and to any serm comparison study evaluating HPG axis stimulation.

Regulatory status as of 2026 remains investigational for enclomiphene as a standalone agent in most jurisdictions, though research use continues under appropriate institutional frameworks.

The serm, Peptide Interface: Assay Design and Biomarker Interpretation
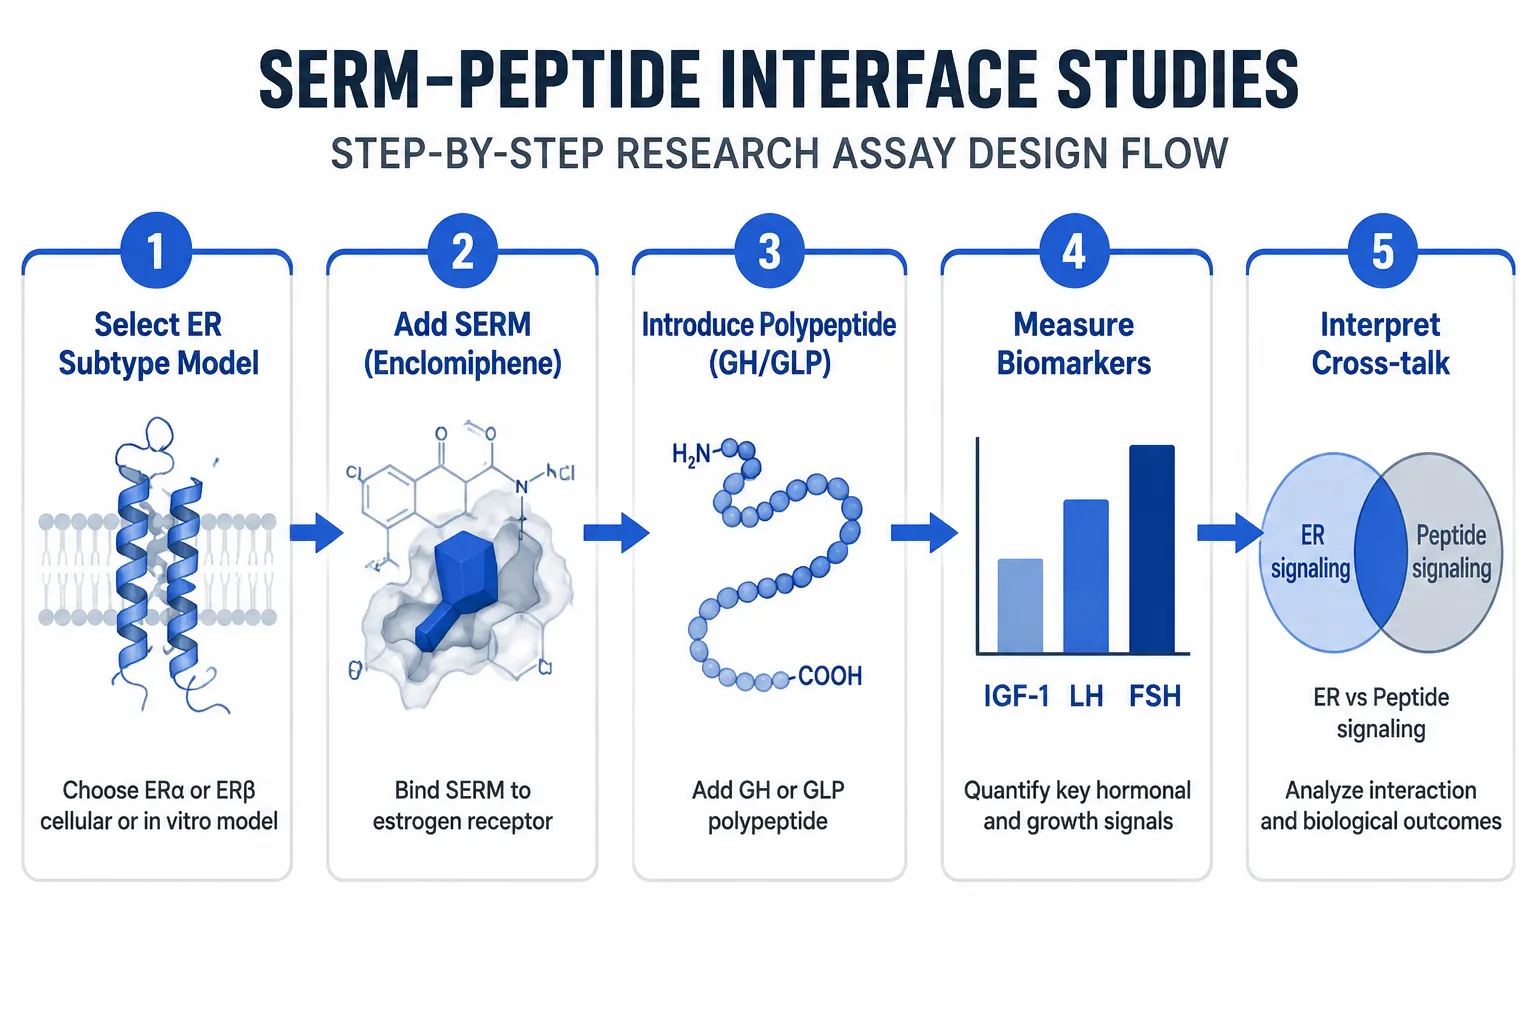
The serm, Peptide Interface: Assay Design and Biomarker Interpretation

This is where Estrogen Receptor Pharmacology, Enclomiphene, and Polypeptide Hormones: A Researcher's Guide to serm, Peptide Interface becomes most practically demanding. When enclomiphene or any serm is co-administered with polypeptide hormones in a research model, at least three layers of interaction require pre-planned biomarker coverage.

Layer 1, HPG Axis Peptide Output

Enclomiphene's antagonism at hypothalamic ERα increases GnRH pulse frequency. This directly elevates LH and FSH, which in turn stimulate testicular steroidogenesis. Researchers co-administering GH secretagogues or systemic peptide research compounds must account for the fact that elevated LH can alter the hormonal milieu in which GH and IGF-1 are being measured.

Recommended baseline biomarkers before serm, peptide co-administration:

  • LH, FSH, total and free testosterone
  • Estradiol (E2), confirms ER blockade efficacy
  • IGF-1, GH axis baseline
  • SHBG, modulates free hormone fractions

Layer 2, Receptor Cross-talk at Target Tissues

Bone, brain, and breast tissue each express combinations of ERα, ERβ, and GPER. GH and GLP-class peptides also act at receptors in these tissues. Overlapping signaling through PI3K/Akt and MAPK pathways means that a serm-induced shift in ER conformation can amplify or attenuate peptide hormone responses at the same downstream node.

For steroidogenesis research models, this cross-talk is especially pronounced in gonadal tissue where both LH-driven steroidogenesis and local ER signaling converge.

Layer 3, Next-Generation ER Agents as Research Variables

SERDs (selective estrogen receptor degraders), PROTACs targeting ER for proteasomal degradation, CERANs (complete estrogen receptor antagonists), and SERCAs (selective ER covalent antagonists) are increasingly present in translational research pipelines as of 2026. Unlike enclomiphene, which modulates receptor conformation, SERDs and PROTACs reduce receptor protein levels entirely. This fundamentally changes baseline ER availability when peptide co-administration begins, requiring separate receptor quantification steps in the assay protocol.

Researchers building multi-compound models should consult translational research design frameworks to pre-specify which ER measurement endpoints will be collected at each timepoint.

Practical Assay Checklist

  • Map ER subtype expression in the target tissue before compound introduction
  • Establish serm washout periods appropriate to the isomer's half-life
  • Use multiplexed immunoassay panels to capture LH, FSH, IGF-1, and E2 simultaneously
  • Include vehicle-only and peptide-only control arms to isolate serm contribution
  • Validate peptide compound purity through independent analysis, compound quality directly affects signal interpretation

Conclusion

Estrogen Receptor Pharmacology, Enclomiphene, and Polypeptide Hormones: A Researcher's Guide to serm, Peptide Interface converges on one central principle: receptor subtype specificity is not optional when peptide hormones share the experimental environment. Enclomiphene's clean ER antagonism at the HPG axis makes it a valuable research tool precisely because it avoids the estrogenic noise of racemic clomiphene, but that advantage is only realized when assay design accounts for downstream peptide hormone interactions.

Actionable next steps for researchers in 2026:

  1. Profile ER subtype expression in your target tissue before any co-administration protocol.
  2. Choose enclomiphene over racemic clomiphene when a pure HPG axis stimulus is required.
  3. Build multiplexed biomarker panels that capture both ER-mediated and peptide-mediated endpoints simultaneously.
  4. Account for next-generation ER agents (SERDs, PROTACs) as distinct variables that alter receptor availability, not just conformation.
  5. Source research compounds with verified purity, impure peptide preparations introduce confounders that no statistical correction can fully remove.

The serm, peptide interface is one of the most mechanistically rich areas in current endocrine research. Rigorous design at this intersection does not just improve data quality, it makes the science translatable.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/estrogen-receptor-pharmacology-enclomiphene-and-polypeptide-hormones-a-researche.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-05 13:05:572026-09-05 13:05:57Estrogen Receptor Pharmacology, Enclomiphene, and Polypeptide Hormones: A Researcher’s Guide to serm–Peptide Interface
Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies

Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies

September 3, 2026/0 Comments/in Uncategorized/by

A PSA reading below 0.2 ng/mL within nine months of starting androgen deprivation therapy now ranks as one of the strongest independent predictors of long-term survival in hormone-sensitive prostate cancer research. That single data point illustrates why understanding Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies matters to anyone working in or following endocrine and oncology research.

Key Takeaways

  • PSA is a serine protease polypeptide and a primary efficacy endpoint in hormone and serm-related prostate research.
  • Research labs routinely pair PSA with testosterone, LH, and FSH to build a complete hormonal picture.
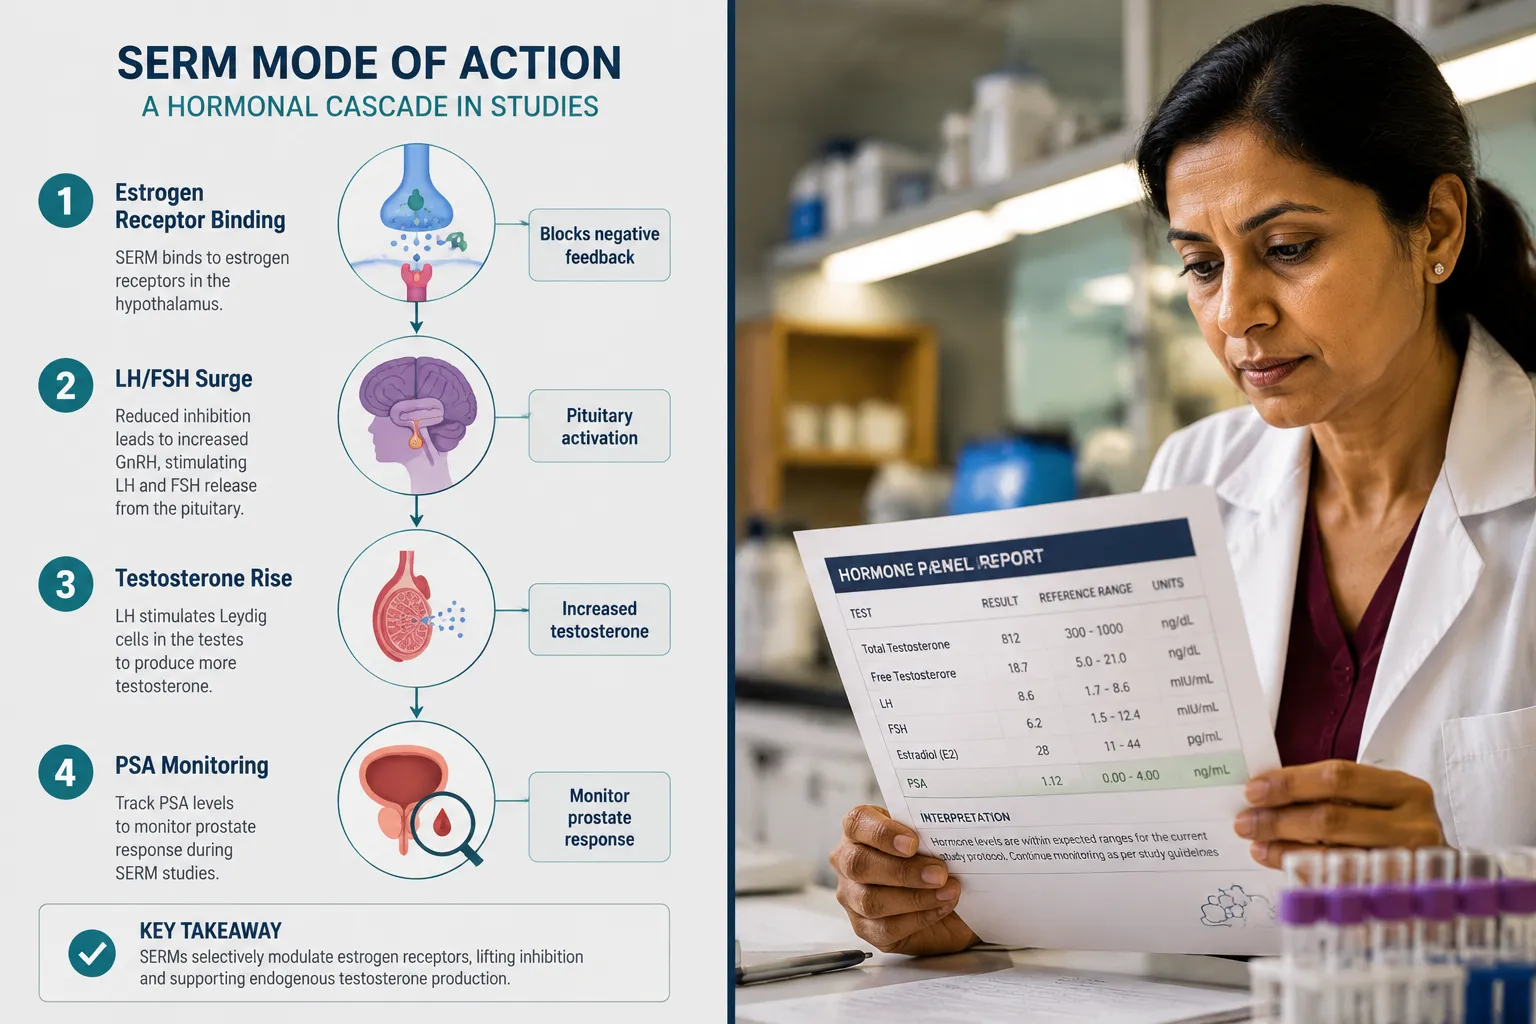
  • serm compounds, including enclomiphene, raise LH and FSH, which in turn elevates testosterone and can influence PSA levels.
  • Novel PSA indices such as the initial-to-nadir PSA ratio are emerging as independent predictors of treatment response.
  • Peptide and polypeptide hormone panels are expanding beyond PSA alone, integrating PSMA metrics and growth hormone secretagogue markers in translational trials.

What PSA Actually Is: A Polypeptide at the Center of Hormone Research

What PSA Actually Is: A Polypeptide at the Center of Hormone Research

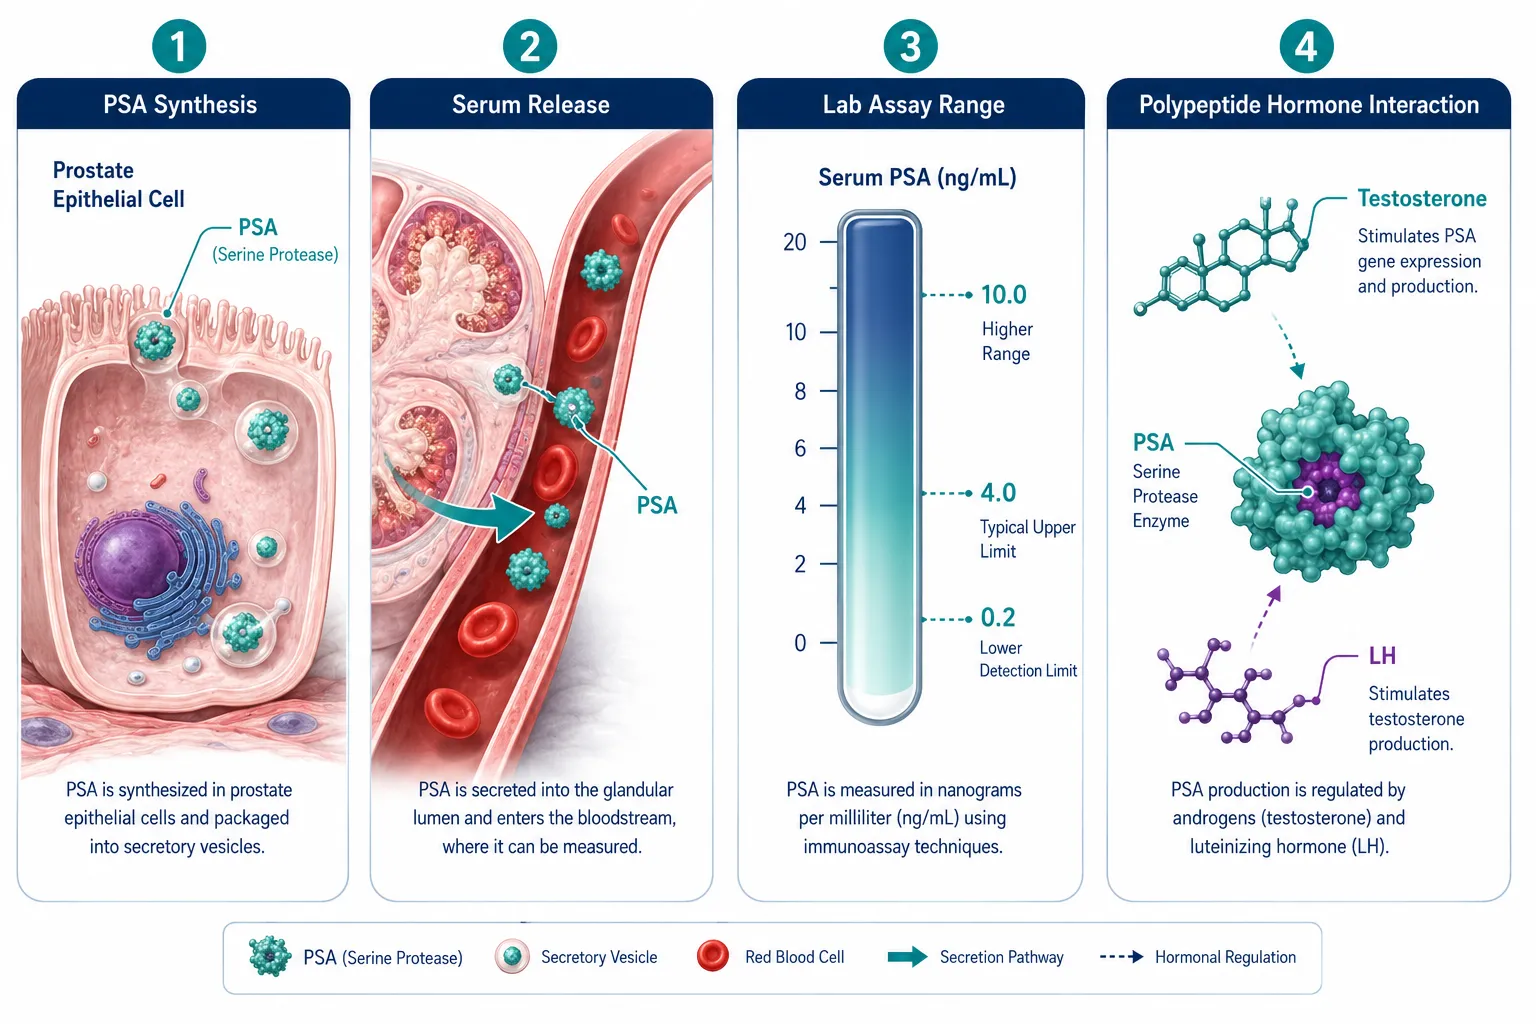
Prostate-specific antigen is not merely a cancer screening number. It is a 237-amino-acid serine protease,a polypeptide produced primarily by prostate epithelial cells and regulated by androgenic signaling. Because testosterone and dihydrotestosterone directly stimulate PSA gene transcription via androgen receptor binding, PSA functions as a sensitive downstream readout of androgen activity. This makes it indispensable in any study that manipulates the hormonal axis.

In the context of Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies, PSA occupies a unique position: it is itself a polypeptide, it responds to polypeptide hormones such as luteinizing hormone (LH) and follicle-stimulating hormone (FSH), and it serves as the primary efficacy biomarker in androgen deprivation therapy (ADT) and androgen receptor pathway inhibitor (ARPI) trials.

Key polypeptide hormones measured alongside PSA in standard research panels include:

  • LH and FSH, pituitary glycoprotein hormones that regulate gonadal testosterone output
  • Testosterone (total and free), the primary androgenic driver of PSA expression
  • Sex hormone-binding globulin (SHBG), a transport protein that modulates free testosterone availability
  • Growth hormone and IGF-1, relevant in systemic peptide research that intersects with prostate biology

How serm Pharmacology Connects to PSA Monitoring

How serm Pharmacology Connects to PSA Monitoring

Selective estrogen receptor modulators (serms) such as enclomiphene, tamoxifen, and clomiphene block estrogen receptors in the hypothalamus and pituitary. This blockade removes negative feedback on GnRH pulsatility, causing a rise in LH and FSH, which then stimulates testicular testosterone production. Because PSA is androgen-sensitive, any intervention that raises testosterone carries the potential to shift PSA levels, a critical consideration in research design.

Understanding serm pharmacology is therefore inseparable from understanding PSA dynamics. Labs conducting serm research on male hypogonadism or testosterone restoration protocols routinely include PSA as a safety and efficacy endpoint precisely because of this hormonal cascade.

"In hormone and serm studies, PSA is not just a prostate cancer marker, it is a functional readout of androgenic activity across the entire hypothalamic-pituitary-gonadal axis."

A well-designed serm comparison study will typically measure:

Biomarker Role in Study
PSA (ng/mL) Primary safety and efficacy endpoint
Total testosterone Confirms androgenic response
LH and FSH Validates serm mechanism of action
Estradiol Monitors estrogenic rebound
SHBG Contextualizes free testosterone changes

The ARANOTE trial, which evaluated darolutamide combined with ADT, used undetectable PSA (below 0.2 ng/mL) as its key efficacy marker. Real-world cohort data confirm that PSA at six to twelve months of ADT plus ARPI predicts survival outcomes and guides decisions on treatment escalation or de-escalation.

What Research Labs Measure: The Full Panel in Hormone and serm Studies

What Research Labs Measure: The Full Panel in Hormone and serm Studies

The scope of Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies has expanded considerably in 2026. Beyond the classic PSA-plus-testosterone panel, modern translational trials incorporate several additional metrics.

Novel PSA Indices

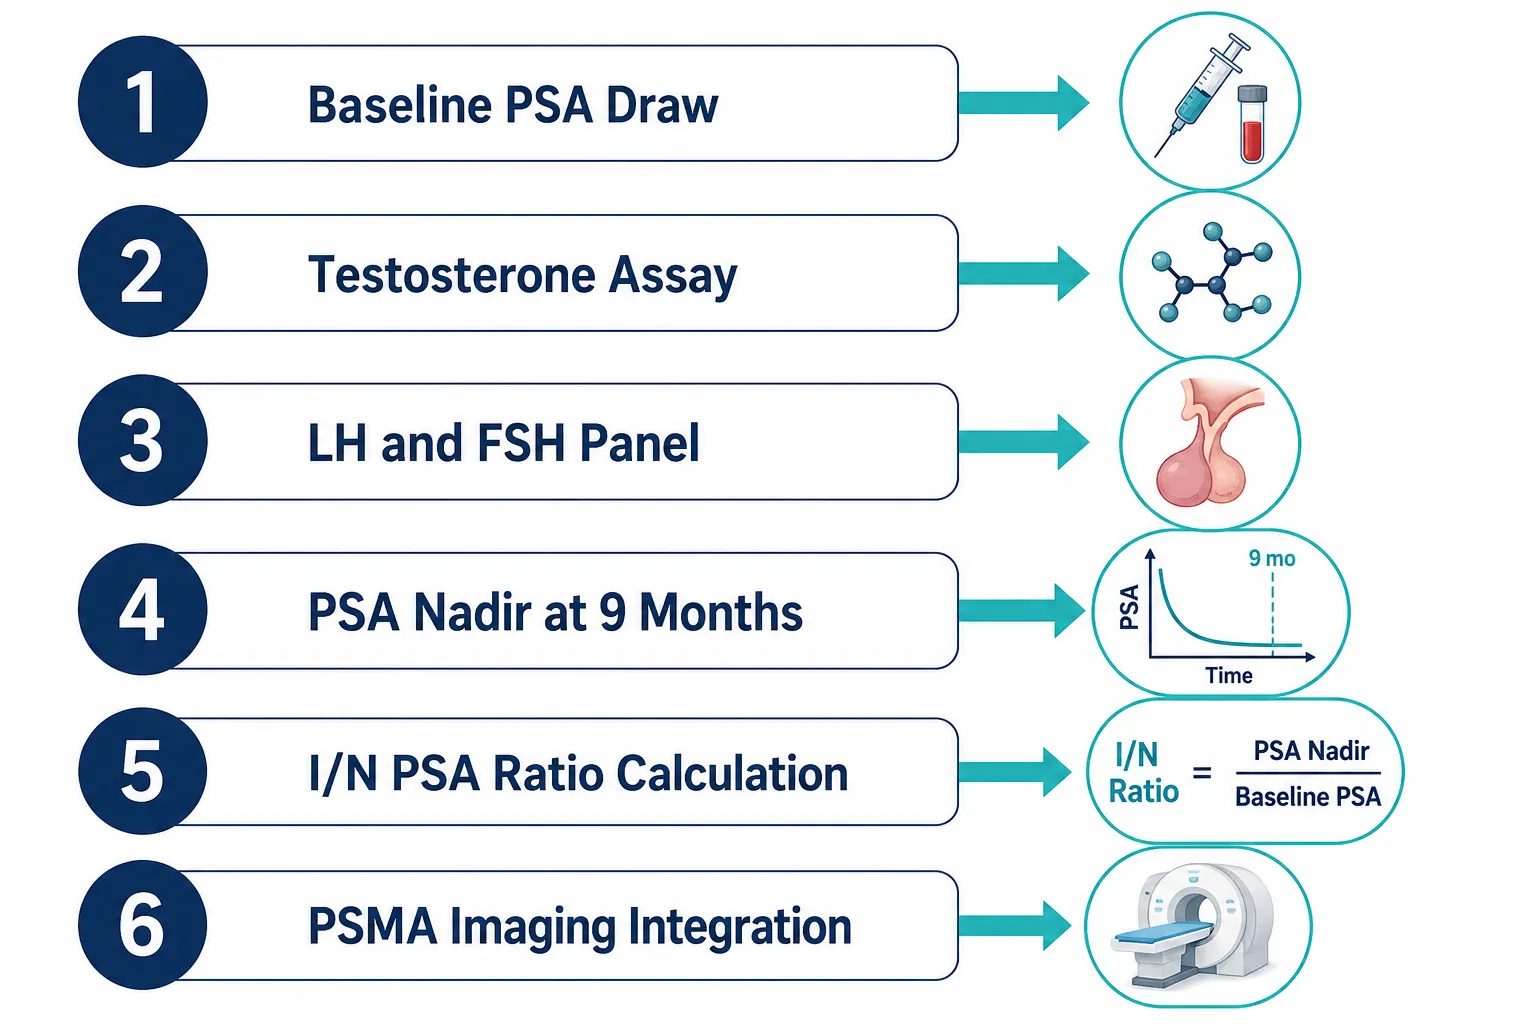
The initial-to-nadir PSA ratio (I/N PSA) has emerged as an independent predictor of both treatment response and overall survival. Labs calculate this by dividing the baseline PSA by the lowest PSA achieved during therapy. A steep ratio signals robust androgen suppression and correlates with improved outcomes in ADT-treated cohorts.

PSA variability and repeat testing protocols have also received renewed attention. Screening analyses confirm that a single PSA draw carries meaningful biological variability, making serial measurements and standardized collection intervals essential for reliable research endpoints.

Integrating PSMA Metrics

Prostate-specific membrane antigen (PSMA) radioligand therapy trials such as the ENZA-p study now integrate both PSA and PSMA imaging metrics. PSMA is itself a transmembrane peptide, and its expression correlates with, but is not identical to, PSA levels. Labs running hormone-refractory disease studies must therefore treat PSA and PSMA as complementary rather than interchangeable endpoints.

Peptide Hormones in Growth Axis Research

Researchers exploring growth hormone secretagogues such as those studied in sermorelin, ipamorelin, and CJC-1295 protocols measure IGF-1 and growth hormone pulse amplitude alongside PSA when subjects are older males. This overlap reflects the broader principle that no single peptide or hormone acts in isolation. Translational research design increasingly demands multi-analyte panels that capture hormonal crosstalk.

For labs exploring mitochondria-targeted peptides, resources such as SS-31 mechanism and research highlight how oxidative stress markers can complement hormone panels in aging-related studies.

ADT-Sparing Strategies and PSA Thresholds

Emerging ADT-sparing research uses PSA as the primary marker for determining whether lifelong castration can be avoided. Guideline and cohort data now define specific PSA thresholds for initiating and timing ADT after local treatment relapse. The PSA-response-adapted radiation approach tested in the RANGER phase II trial exemplifies how a single polypeptide biomarker can drive individualized treatment algorithms.

Conclusion

The relationship between Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies is more integrated than most summaries suggest. PSA is simultaneously a polypeptide product, an androgen-axis readout, and a safety endpoint in serm and hormone research. Labs that treat it as a standalone number miss the broader hormonal narrative.

Actionable next steps for researchers and lab professionals:

  1. Adopt serial PSA measurement protocols with standardized intervals rather than relying on single-draw values.
  2. Pair PSA with LH, FSH, total testosterone, and SHBG to capture the full hormonal axis in serm and ADT studies.
  3. Calculate the I/N PSA ratio as a supplementary predictor of response and survival in ADT-treated cohorts.
  4. Integrate PSMA imaging data in hormone-refractory protocols to avoid over-relying on PSA alone.
  5. Review current serm research and translational research design frameworks to ensure multi-analyte panels reflect 2026 guideline updates.

Staying current with how PSA interacts with the broader peptide and polypeptide hormone landscape is no longer optional, it is the baseline standard for credible hormone and serm research design.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-peptides-and-polypeptide-hormones-what-research-labs-m.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-03 13:05:362026-09-03 13:05:36Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies
Peptides and Polypeptides in Endocrine Pharmacology: How Enclomiphene Interfaces With Estrogen Receptor Biology

Peptides and Polypeptides in Endocrine Pharmacology: How Enclomiphene Interfaces With Estrogen Receptor Biology

August 1, 2026/0 Comments/in Uncategorized/by

Fewer than 10% of clinicians who prescribe selective estrogen receptor modulators can accurately define the structural difference between a peptide hormone and a small-molecule serm, yet that distinction determines how each drug class reshapes the endocrine axis. Peptides and polypeptides in endocrine pharmacology represent one of the most mechanistically rich areas of modern pharmacology, and understanding where non-peptide agents like enclomiphene fit within that landscape is essential for anyone conducting or interpreting research in this field.

Key Takeaways

  • Peptide and polypeptide hormones act on cell-surface receptors through second-messenger cascades, while enclomiphene binds directly inside the nucleus at estrogen receptors.
  • Enclomiphene works as an estrogen receptor antagonist at the hypothalamus, disrupting negative feedback and increasing endogenous LH and FSH secretion.
  • The hypothalamic-pituitary-gonadal (HPG) axis is the shared regulatory highway for both peptide-based and small-molecule endocrine modulators.
  • Purity and characterization of research compounds, whether peptide or small molecule, directly affect the reliability of mechanistic data.
  • Combining knowledge of peptide receptor biology with serm pharmacology produces a more complete picture of hormonal signaling networks.

The Structural Divide: Peptide Hormones Versus Small-Molecule Modulators

To appreciate how enclomiphene interfaces with estrogen receptor biology, it helps to first anchor the broader category of peptides and polypeptides in endocrine pharmacology.

Peptide hormones are chains of amino acids. Short chains of 2-50 residues are typically called peptides; longer chains become polypeptides and, eventually, proteins. Examples include gonadotropin-releasing hormone (GnRH), luteinizing hormone (LH), follicle-stimulating hormone (FSH), and growth hormone-releasing hormone (GHRH). These molecules are too large and too hydrophilic to cross the cell membrane, so they bind to surface receptors and trigger intracellular signaling cascades, most commonly through cyclic AMP or phospholipase C pathways.

Research into peptide modulators spans a wide range of targets. For instance, BPC-157 and TB-500 peptide research explores tissue-signaling mechanisms that share conceptual overlap with endocrine feedback loops. Similarly, GLP-1 peptide sourcing and research illustrates how incretin-class peptides modulate metabolic signaling through surface-receptor mechanisms, a useful structural contrast to nuclear receptor pharmacology.

Small-molecule agents like enclomiphene are chemically synthesized, low-molecular-weight compounds. They are lipophilic enough to diffuse across cell membranes and interact directly with intracellular receptors, in this case, the estrogen receptor (ER), a nuclear receptor superfamily member.

"The key pharmacological divide is not potency, it is receptor location. Peptide hormones knock on the cell's front door; small-molecule serms walk straight into the nucleus."

The Structural Divide: Peptide Hormones Versus Small-Molecule Modulators

How Enclomiphene Interfaces With Estrogen Receptor Biology Within the HPG Axis

The hypothalamic-pituitary-gonadal (HPG) axis is the shared regulatory highway where both peptide hormones and small-molecule modulators exert their effects.

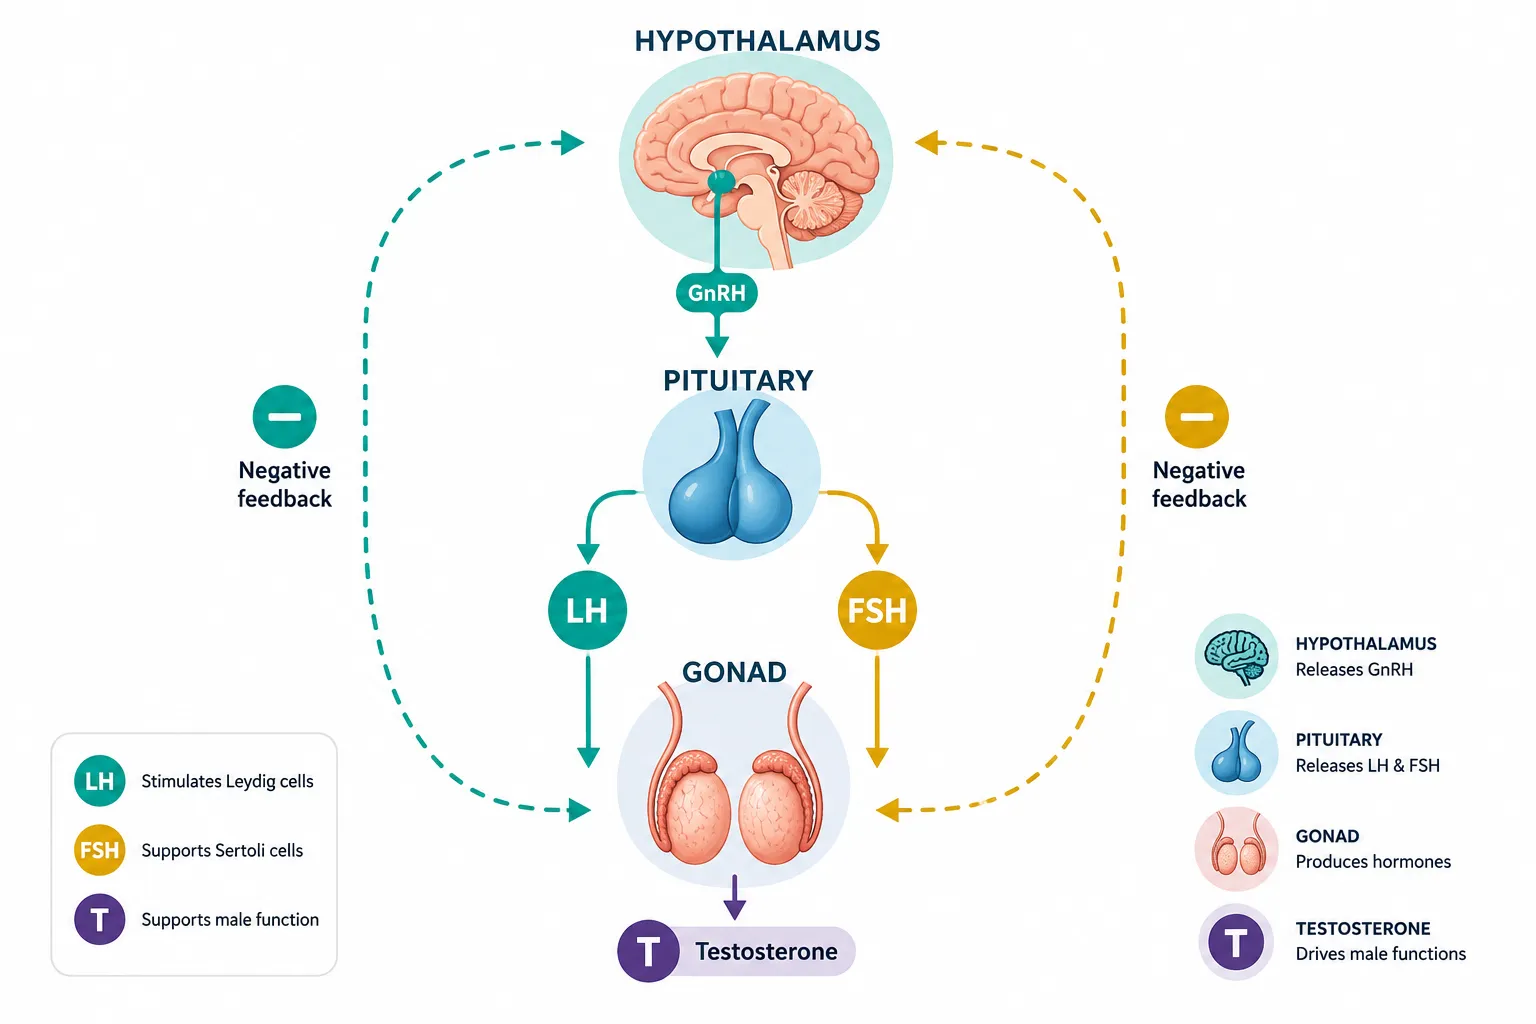
Under normal physiology, circulating estradiol binds to estrogen receptors in hypothalamic neurons and pituitary gonadotrophs. This binding suppresses GnRH pulse frequency and reduces LH and FSH secretion, a classic negative-feedback loop mediated by a steroid hormone acting on nuclear receptors.

Enclomiphene, the trans-isomer of clomiphene citrate, competitively occupies estrogen receptors at these same hypothalamic and pituitary sites. Because it acts as a selective estrogen receptor antagonist in these tissues, it blocks estradiol's inhibitory signal. The hypothalamus interprets this blockade as low circulating estrogen, responds by increasing GnRH pulse amplitude, and the pituitary responds with elevated LH and FSH output.

The downstream result is stimulation of endogenous gonadal steroidogenesis, a fundamentally different mechanism from direct peptide hormone replacement. Compare this to tesa, a synthetic GHRH analog that binds surface receptors on pituitary somatotrophs to stimulate growth hormone release. Both agents ultimately raise a downstream hormone, but through entirely different receptor classes and cellular compartments.

Tissue-Selective Receptor Modulation

Enclomiphene's selectivity is tissue-dependent. In the hypothalamus and pituitary, it behaves as an antagonist. In other tissues, such as bone, estrogenic agonist activity may be partially preserved. This tissue selectivity is what defines the broader serm class and distinguishes these agents from pure estrogen blockers.

Feature Peptide Hormones Enclomiphene (serm)
Receptor location Cell surface Nuclear (intracellular)
Mechanism Second-messenger cascade Direct DNA transcription modulation
Tissue selectivity Determined by receptor subtype Determined by co-activator expression
Route of action Extracellular binding Intracellular ligand-binding domain

Peptides and Polypeptides in Endocrine Pharmacology: Research Sourcing and Compound Integrity

Peptides and Polypeptides in Endocrine Pharmacology: Research Sourcing and Compound Integrity

Peptides and Polypeptides in Endocrine Pharmacology: Research Sourcing and Compound Integrity

For researchers working across both peptide and small-molecule endocrine pharmacology, compound purity is a non-negotiable variable. Mechanistic studies that use impure or mischaracterized compounds produce data that cannot be replicated or translated.

This principle applies equally to peptide-based endocrine research tools. The GHK-Cu copper peptide research and sourcing guide addresses quality benchmarks relevant to any peptide used in signaling research. Likewise, the BPC-157 core documentation and first research guide outlines documentation standards that set a useful precedent for characterizing any endocrine research compound.

When sourcing peptides for studies that sit adjacent to serm pharmacology research, for example, examining GnRH analog interactions or LH pulse dynamics, researchers benefit from working with lab-tested peptides that carry third-party certificates of analysis. The same rigor should be applied to any small-molecule comparator used in parallel assays.

Three sourcing standards that apply across compound classes:

  1. Certificate of Analysis (CoA), confirms identity and purity by HPLC and mass spectrometry
  2. Sterility testing, essential for any in vivo research application
  3. Stability data, particularly relevant for peptides, which degrade faster than most small molecules under improper storage conditions

For researchers exploring the growth hormone-releasing axis alongside HPG axis modulators, resources on GHRP-2 versus sermorelin provide useful mechanistic context on how peptide secretagogues differ from receptor-level modulators like enclomiphene.

Conclusion

Peptides and polypeptides in endocrine pharmacology and small-molecule agents like enclomiphene occupy different receptor compartments, but they converge on the same hormonal axes. Enclomiphene's antagonism at hypothalamic and pituitary estrogen receptors reshapes the HPG axis through nuclear receptor biology, a mechanism that is structurally and functionally distinct from the surface-receptor signaling used by GnRH, LH, FSH, and synthetic peptide analogs.

Actionable next steps for researchers:

  • Map the receptor class (surface vs. nuclear) of every agent used in an endocrine study before designing assays.
  • Source all peptide and small-molecule research compounds with documented CoA, sterility, and stability data.
  • When studying HPG axis dynamics, consider how serm-mediated changes in gonadotropin output interact with any co-administered peptide modulators.
  • Review mechanistic literature on tissue-selective ER modulation to contextualize enclomiphene's differential effects across target tissues.

Understanding the structural and mechanistic divide between peptide hormones and nuclear receptor modulators is not academic trivia, it is the foundation of reproducible, translatable endocrine pharmacology research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/peptides-and-polypeptides-in-endocrine-pharmacology-how-enclomiphene-interfaces.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-01 13:04:512026-08-01 13:04:51Peptides and Polypeptides in Endocrine Pharmacology: How Enclomiphene Interfaces With Estrogen Receptor Biology

Tag Archive for: serm pharmacology

Estrogen Receptor Signaling and Enclomiphene: Linking Classic Endocrine Pharmacology to Modern serm Research Models

Estrogen Receptor Signaling and Enclomiphene: Linking Classic Endocrine Pharmacology to Modern serm Research Models

July 15, 2026/0 Comments/by Pure Tested

Fewer than 5% of men diagnosed with secondary hypogonadism are offered alternatives to exogenous testosterone replacement, yet enclomiphene, a single stereoisomer of clomiphene, has drawn sustained attention in research circles precisely because it targets the same estrogen receptor signaling axis that endocrinologists have studied for decades. Understanding estrogen receptor signaling and enclomiphene: linking classic endocrine pharmacology to modern serm research models requires tracing a path from foundational receptor biology to today's selective estrogen receptor modulator (serm) science.

Key Takeaways

  • Enclomiphene is the trans-isomer of clomiphene and acts as an estrogen receptor antagonist at the hypothalamic-pituitary level.
  • By blocking estrogen negative feedback, enclomiphene stimulates LH and FSH release, which in turn supports endogenous testosterone production.
  • Legacy serms such as tamoxifen and raloxifene established the receptor-binding framework that modern enclomiphene research builds upon.
  • Tissue-selective receptor modulation distinguishes serms from both full agonists and pure antagonists.
  • Enclomiphene research fits within a broader landscape of endocrine-modulating compounds studied alongside peptide-based secretagogues and metabolic agents.

Key Takeaways

How Estrogen Receptor Signaling Governs the HPG Axis

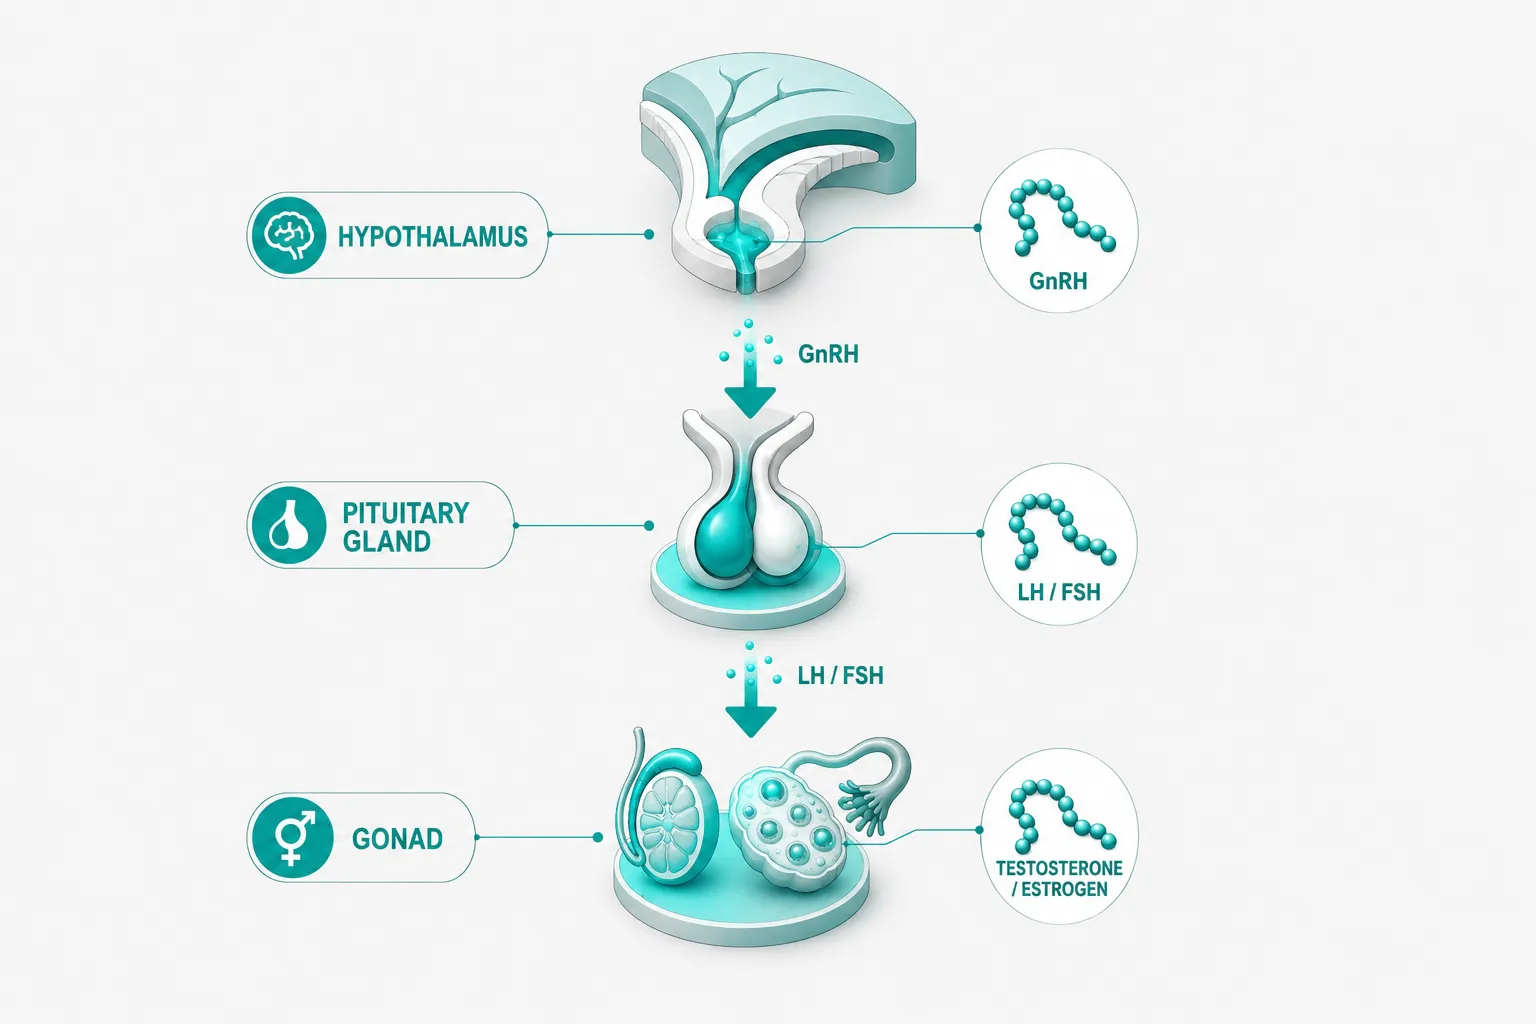
The hypothalamic-pituitary-gonadal (HPG) axis operates through a tightly regulated feedback loop. The hypothalamus releases gonadotropin-releasing hormone (GnRH), which prompts the anterior pituitary to secrete luteinizing hormone (LH) and follicle-stimulating hormone (FSH). These gonadotropins then stimulate gonadal steroidogenesis, testosterone production in males, estradiol and progesterone in females.

Estrogen receptor alpha (ERα) plays a central role in this loop. When circulating estradiol binds ERα at hypothalamic neurons, it suppresses GnRH pulse frequency, reducing downstream LH and FSH. This negative feedback is the primary target of serm pharmacology.

Key receptor-level concepts researchers track:

  • Ligand-binding domain (LBD) conformation, determines whether a compound acts as agonist or antagonist
  • Coactivator vs. corepressor recruitment, drives tissue-specific gene transcription
  • ERα vs. ERβ selectivity, explains differential effects across bone, breast, uterine, and neural tissue

This framework, established through decades of tamoxifen and raloxifene research, is the same scaffold used when evaluating enclomiphene in preclinical and clinical models. Researchers exploring related neuroendocrine and innate immunity pathways will recognize how tightly hormonal and immune signaling are intertwined at the receptor level.


Legacy serms vs. Enclomiphene: A Pharmacological Contrast

Legacy serms vs. Enclomiphene: A Pharmacological Contrast

Tamoxifen, introduced in the 1970s, was the first clinically significant serm. Raloxifene followed, offering improved bone and cardiovascular profiles. Clomiphene citrate, a racemic mixture of zuclomiphene (cis) and enclomiphene (trans), became standard for ovulation induction.

"Enclomiphene's pharmacological advantage lies in its shorter half-life and cleaner receptor profile compared to the racemic parent compound."

The table below summarizes key distinctions:

Compound Primary Target Half-Life Key Research Use
Tamoxifen ERα (breast) ~5-7 days Oncology models
Raloxifene ERα/ERβ (bone) ~28 hours Osteoporosis research
Clomiphene (racemic) Hypothalamic ERα ~5-7 days Ovulation induction
Enclomiphene Hypothalamic ERα ~10 hours Male HPG axis research

Enclomiphene's shorter half-life reduces receptor occupancy duration, which researchers hypothesize may lower the risk of prolonged estrogenic side effects seen with zuclomiphene accumulation. Those studying IPA serm stack research will find this receptor-selectivity distinction directly relevant to how serms are combined with growth hormone secretagogues in research protocols.


Enclomiphene in Modern serm Research Models

Enclomiphene in Modern serm Research Models

Modern research into estrogen receptor signaling and enclomiphene: linking classic endocrine pharmacology to modern serm research models has moved beyond simple agonist/antagonist labeling. Current models examine:

  1. Pulse dynamics, how enclomiphene alters GnRH pulse frequency in ex-vivo hypothalamic preparations
  2. Receptor occupancy kinetics, binding affinity data compared to endogenous estradiol
  3. Downstream steroidogenesis, LH-driven Leydig cell testosterone output in preclinical models
  4. Metabolic co-effects, interactions with insulin sensitivity and lipid metabolism markers

This last point connects enclomiphene research to a wider metabolic research landscape. Investigators studying metabolic modulation research lines or AOD-9604 metabolic research often encounter overlapping endpoints, since testosterone and growth hormone axes share downstream metabolic effectors.

Enclomiphene is also being contrasted with small-molecule approaches, including statins, which modestly influence testosterone biosynthesis through cholesterol substrate effects, to isolate receptor-mediated from substrate-mediated hormonal changes. This distinction matters when designing clean research models.

For researchers sourcing reference-grade compounds, the serm 10mg research compound page provides purity and specification data relevant to in-vitro and preclinical study design.

Broader endocrine research often pairs serm compounds with secretagogue stacks. The IPA sermorelin stack research context illustrates how HPG-axis and GH-axis modulation are studied in parallel, since both systems converge on body composition and metabolic outcomes. Similarly, longevity peptide research increasingly incorporates hormonal axis optimization as a foundational variable.


Conclusion

Estrogen receptor signaling and enclomiphene: linking classic endocrine pharmacology to modern serm research models is not a niche academic exercise, it is a convergence point for reproductive endocrinology, metabolic biology, and precision pharmacology. Researchers in 2026 have access to a far richer mechanistic toolkit than the tamoxifen era provided.

Actionable next steps for researchers:

  • Map ERα and ERβ expression profiles in target tissues before designing serm intervention studies
  • Use enclomiphene's short half-life as a variable to study pulse-dependent vs. tonic receptor occupancy effects
  • Compare HPG-axis outcomes alongside metabolic markers to capture full-system responses
  • Review compound purity documentation carefully, as stereoisomer contamination confounds receptor-binding data
  • Consider pairing serm research with secretagogue or metabolic peptide protocols to capture cross-axis interactions

The field is moving rapidly. Grounding new enclomiphene research in the deep literature of estrogen receptor pharmacology ensures that modern findings build on, rather than repeat, the foundational work that made serm science possible.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/estrogen-receptor-signaling-and-enclomiphene-linking-classic-endocrine-pharmacol.webp 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-15 13:06:082026-07-20 15:00:06Estrogen Receptor Signaling and Enclomiphene: Linking Classic Endocrine Pharmacology to Modern serm Research Models
Peptides and Polypeptides in Endocrine Research: Linking Estrogen Receptor Signaling to Enclomiphene and GLP-3 Retatrutide Models

Peptides and Polypeptides in Endocrine Research: Linking Estrogen Receptor Signaling to Enclomiphene and GLP-3 Retatrutide Models

June 23, 2026/0 Comments/by Pure Tested

Fewer than three decades ago, the estrogen receptor was considered a single, well-understood target. Today, researchers recognize at least three distinct receptor subtypes — ERalpha, ERbeta, and the G protein-coupled estrogen receptor (GPER) — each capable of driving separate downstream cascades. That complexity is precisely why the field of peptides and polypeptides in endocrine research: linking estrogen receptor signaling to enclomiphene and GLP-3 retatrutide models has become one of the most active areas of translational biology in 2026.

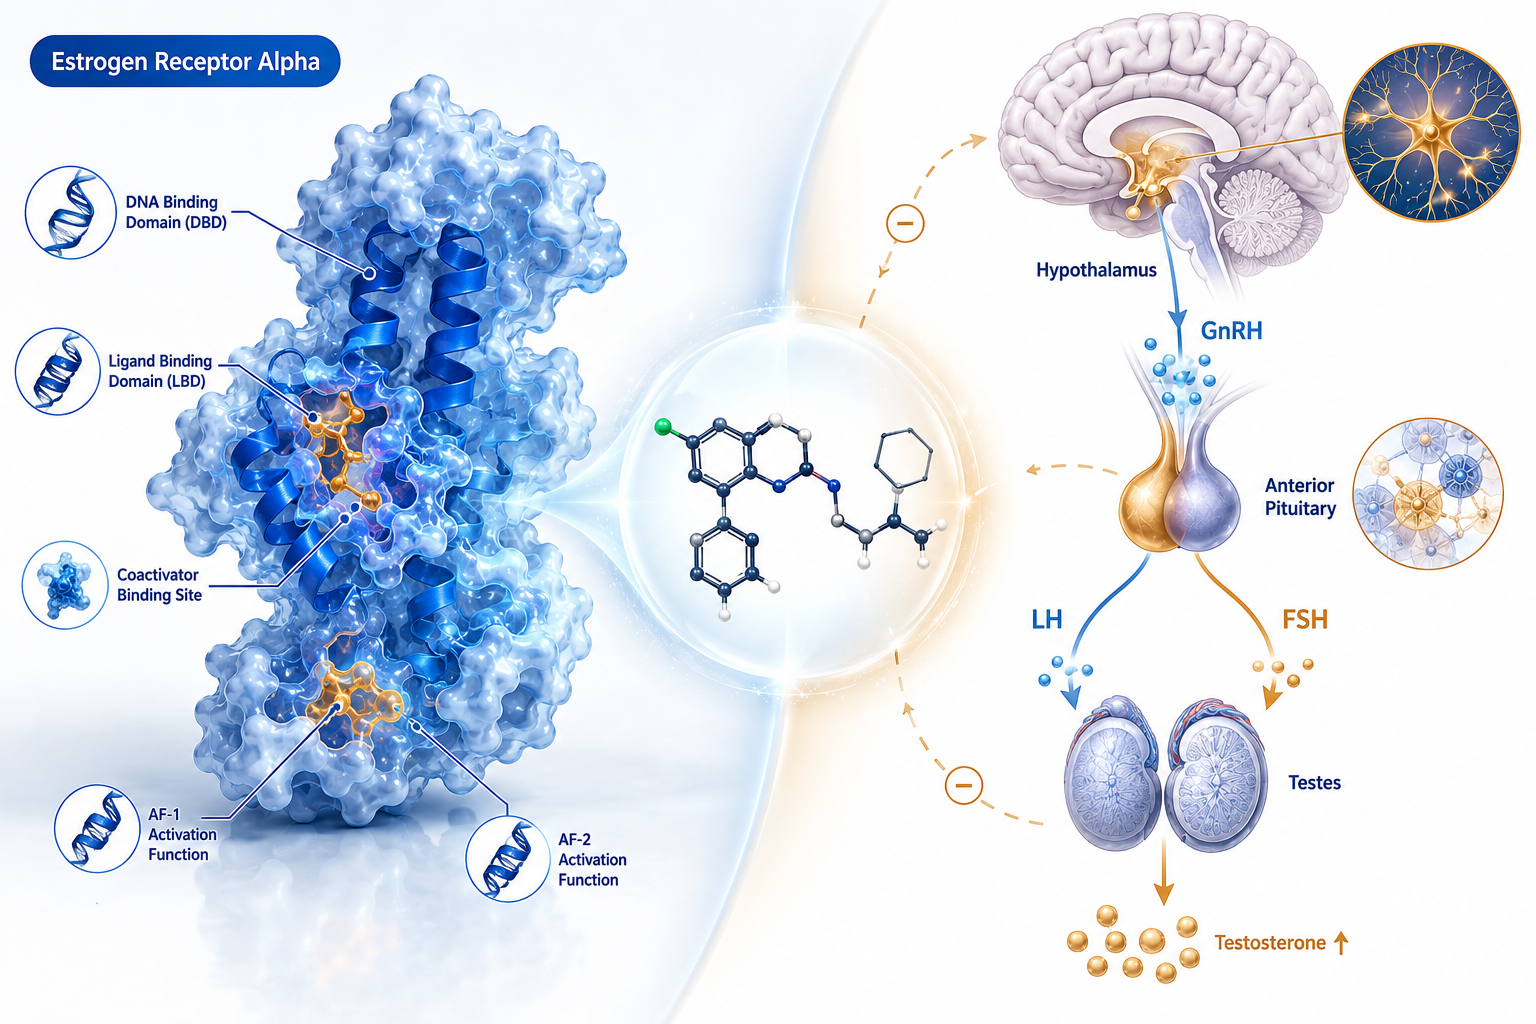
Detailed () scientific illustration showing a split-panel composition: left side features a 3D molecular model of an

Key Takeaways

  • Estrogen receptors are not monolithic; GPER mediates rapid non-genomic signaling distinct from classical nuclear ER pathways.
  • Enclomiphene acts as a selective estrogen receptor modulator (serm) at the hypothalamus, restoring endogenous testosterone without suppressing the HPG axis.
  • Retatrutide is a synthetic 39-amino-acid polypeptide that simultaneously activates GLP-1R, GIPR, and GCGR — a triple-agonist profile unmatched by earlier metabolic peptides.
  • Cross-talk between peptide growth factors and estrogen receptor systems creates layered regulatory complexity relevant to drug design.
  • Both enclomiphene and retatrutide illustrate how modern endocrine research moves beyond single-target pharmacology toward systems-level modulation.

Estrogen Receptor Biology: The Foundation for Peptide Cross-Talk

Classical endocrinology framed estrogen signaling as a nuclear event: ligand binds receptor, receptor binds DNA, gene transcription changes. GPER challenged that model by demonstrating that estrogens also trigger acute, non-genomic responses through G protein-coupled pathways — activating cAMP, mobilizing intracellular calcium, and phosphorylating kinase cascades within minutes rather than hours.

This dual-mode signaling matters for peptide researchers because peptide growth factors and estrogen receptors actively cross-talk. Insulin-like growth factors, epidermal growth factor, and related polypeptides can transactivate ERalpha without a classical estrogen ligand. Conversely, estrogen receptor activity can sensitize cells to peptide growth factor signals. Understanding this bidirectional regulation is foundational to interpreting how newer research compounds interact with hormonal physiology.

"Estrogen receptor cross-talk with peptide signaling systems is not a side effect — it is a core feature of endocrine architecture."

For researchers exploring metabolic and longevity-related peptides, resources such as the MOTS-C metabolic flexibility research overview and the GIP receptor importance guide provide useful context on how peptide signals intersect with broader hormonal networks.


Enclomiphene as a Case Study in Receptor-Selective Endocrine Modulation

Enclomiphene is the trans-isomer of clomiphene and functions as a selective estrogen receptor modulator (serm). Its primary site of action is the hypothalamus and pituitary, where it blocks estrogen receptors and removes the negative-feedback brake on gonadotropin-releasing hormone (GnRH) pulsatility. The result is a cascade: GnRH rises, LH and FSH secretion increases, and the testes respond with elevated testosterone production.

What makes enclomiphene scientifically notable is what it preserves. Unlike exogenous testosterone, enclomiphene leaves the entire hypothalamic-pituitary-gonadal (HPG) axis intact, including its own feedback loops. This distinguishes it sharply from peptide-class HPG stimulators such as gonadorelin or kisspeptin-10, which act at different nodes in the same axis.

Pharmacokinetic profile comparison:

Compound Clearance Axis Preservation
Enclomiphene Days Full HPG axis intact
Zuclomiphene (isomer) Weeks Partial, prolonged suppression risk
Gonadorelin (peptide) Minutes Pulsatile, receptor-dependent

Enclomiphene's rapid clearance — measured in days rather than the weeks seen with its isomer zuclomiphene — makes it a cleaner pharmacological tool for research into upstream estrogen receptor blockade. For comparison, researchers studying GH-axis peptides may find the CJC-1295 and ipamorelin GH axis research a useful parallel for understanding how upstream modulation shapes downstream hormonal output.


GLP-3 Retatrutide Models and the Polypeptide Approach to Metabolic Signaling

GLP-3 Retatrutide Models and the Polypeptide Approach to Metabolic Signaling

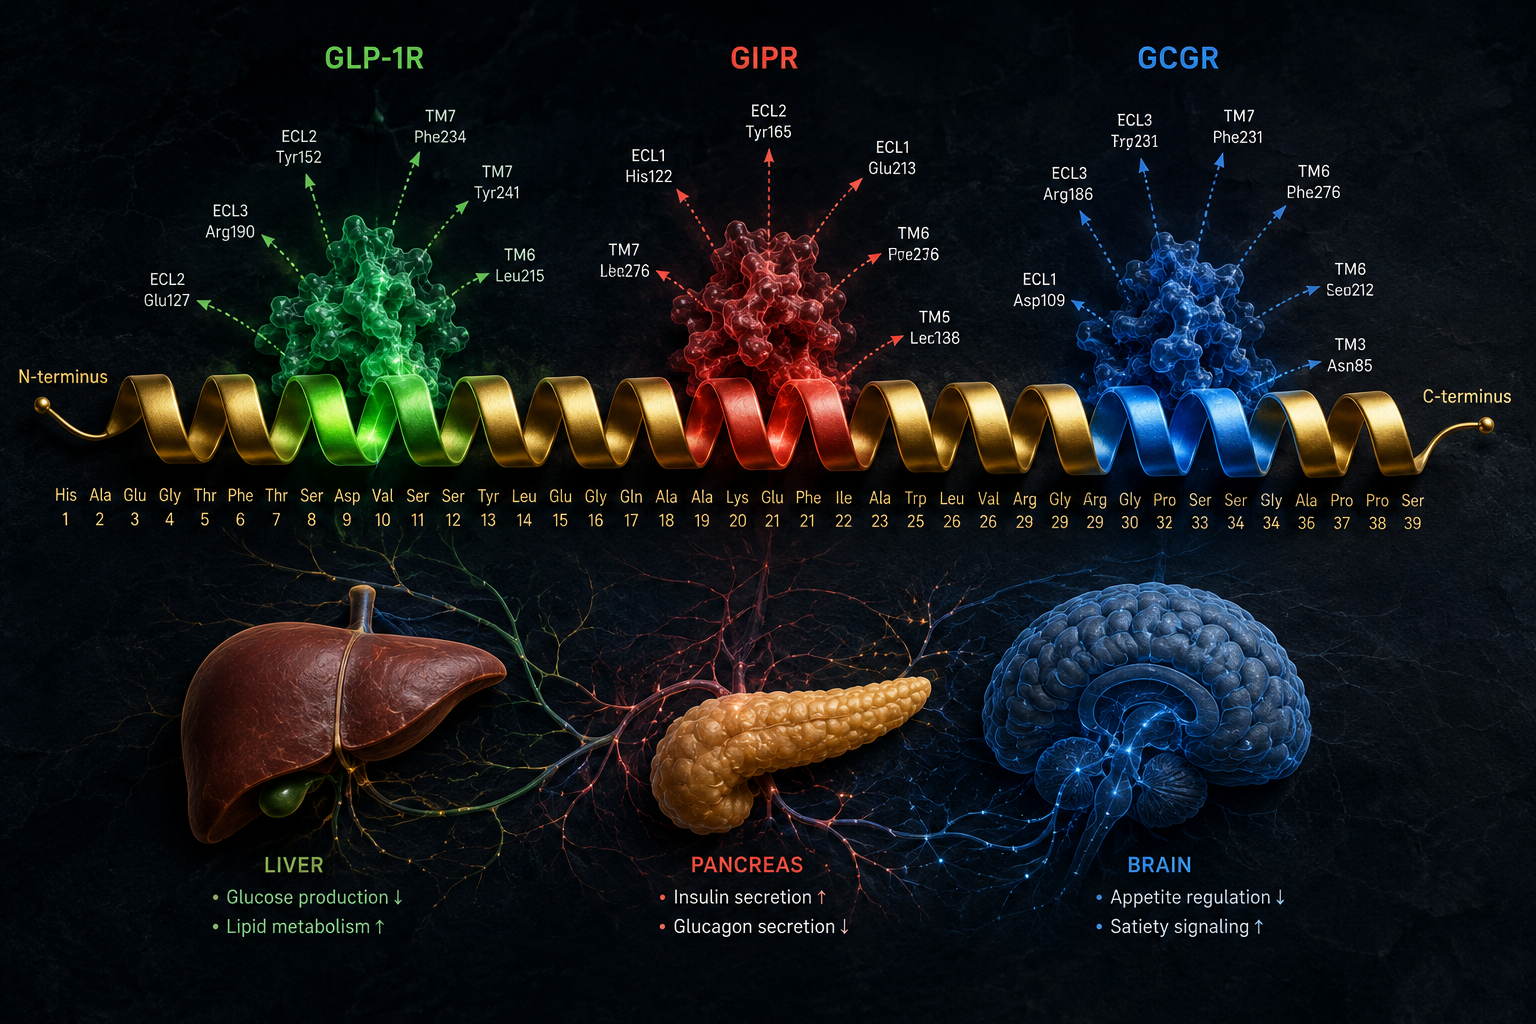
Retatrutide (LY3437943) represents a different philosophy entirely. Rather than blocking a receptor to release a suppressed axis, this synthetic 39-amino-acid polypeptide simultaneously activates three receptors: GLP-1R, GIPR, and GCGR. Cryo-EM structural studies show that retatrutide adopts a single continuous alpha-helix conformation when binding, with receptor-specific amino acid differences accounting for its differential potency at each target.

The coordinated activation of all three receptors produces layered metabolic effects:

  • GLP-1R activation: Reduces food intake, slows gastric emptying, enhances insulin secretion
  • GIPR activation: Amplifies insulin response, modulates adipose tissue signaling
  • GCGR activation: Increases energy expenditure, improves hepatic lipid metabolism

Phase 2 clinical trial data published in 2023 demonstrated significant weight loss and glycemic improvement in participants with obesity and type 2 diabetes. As of 2026, retatrutide has not received regulatory approval for human use and remains within the scope of clinical investigation and preclinical research.

For researchers building context around incretin-based peptide models, the GLP-3 Retatrutide incretin research themes page and the companion GLP-1 incretin research overview offer structured background. The cagrilintide synergy with GLP-1 research further illustrates how dual and triple agonist combinations are reshaping metabolic peptide research.


Bridging the Two Models: What Peptides and Polypeptides in Endocrine Research Reveal

Bridging the Two Models: What Peptides and Polypeptides in Endocrine Research Reveal

The deeper insight from studying peptides and polypeptides in endocrine research: linking estrogen receptor signaling to enclomiphene and GLP-3 retatrutide models together is architectural. Enclomiphene works by subtracting a signal — removing estrogenic feedback — to let a natural axis reassert itself. Retatrutide works by adding multiple signals simultaneously, forcing coordinated receptor activation across organ systems.

Both strategies reflect a move away from single-target pharmacology. Both also interact, directly or indirectly, with estrogen receptor biology. GPER, for instance, has been implicated in metabolic regulation, and GLP-1 receptor signaling has documented interactions with sex hormone pathways in adipose and hepatic tissue.

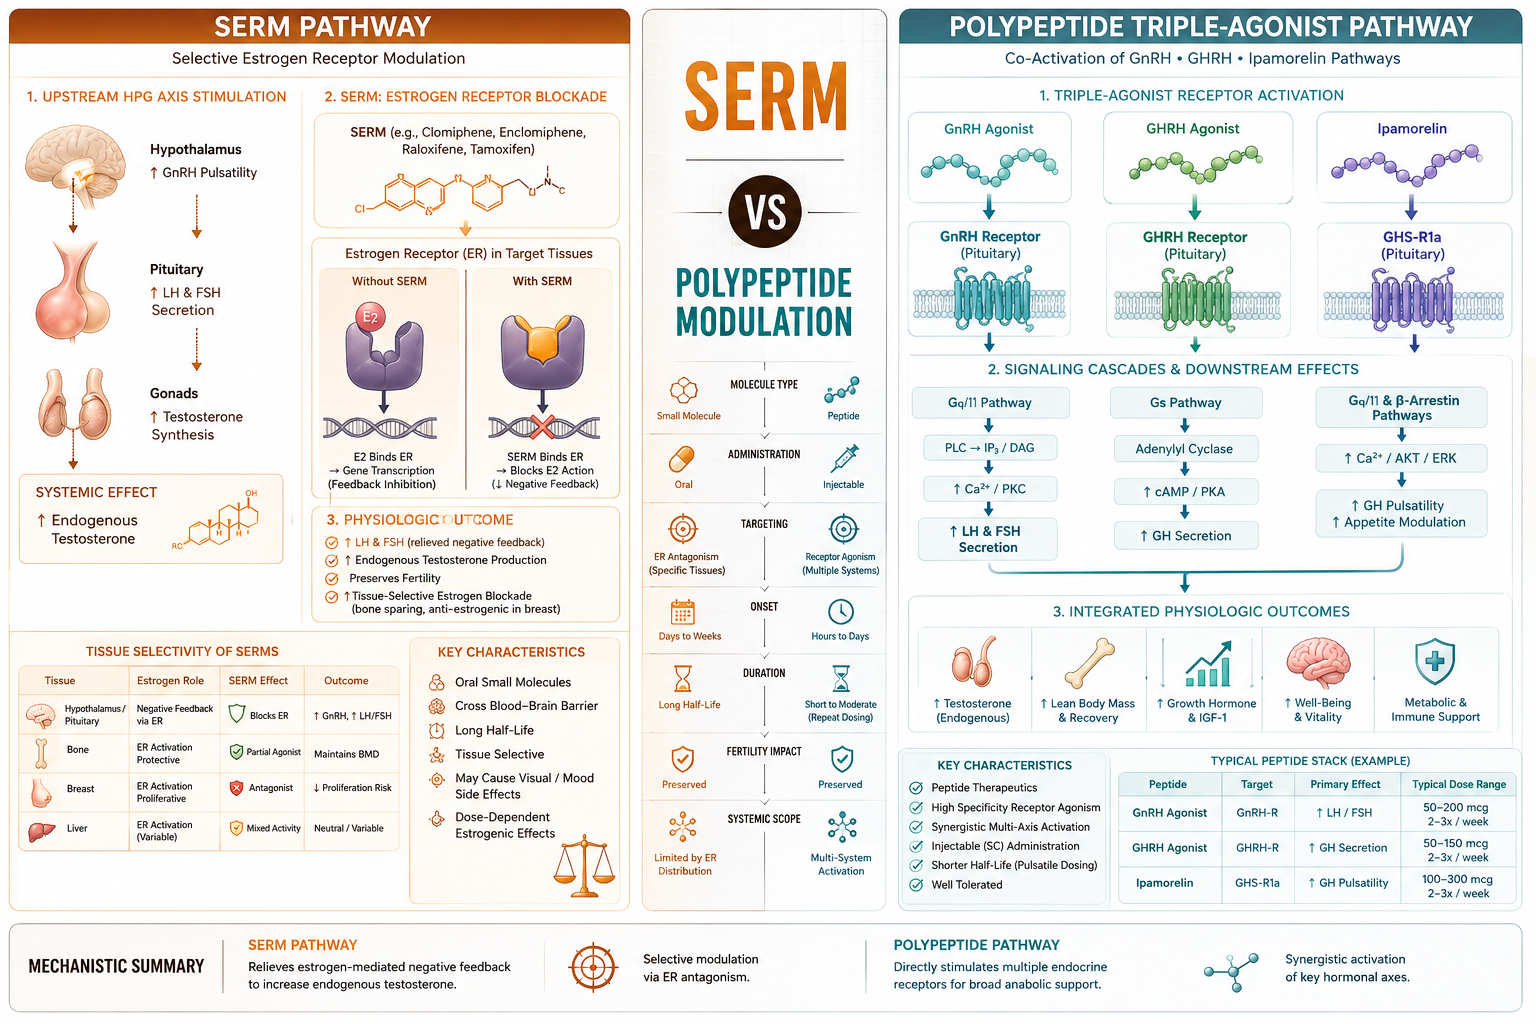
Key distinctions between serm-based and polypeptide-based endocrine modulation:

  • Mechanism: Receptor blockade (serm) vs. receptor co-activation (polypeptide agonist)
  • Axis impact: Preserves negative feedback (enclomiphene) vs. bypasses feedback (retatrutide)
  • Structural class: Small molecule (enclomiphene) vs. synthetic peptide chain (retatrutide)
  • Research maturity: Enclomiphene has longer clinical history; retatrutide is in active Phase 2/3 investigation

Researchers interested in how peptide structural biology shapes receptor selectivity may also find value in reviewing tesa research themes and the IPA muscle and fat research overview, both of which demonstrate how peptide sequence modifications alter tissue-level outcomes.


Conclusion

The convergence of estrogen receptor biology, serm pharmacology, and synthetic polypeptide design represents one of the most productive frontiers in endocrine research today. Enclomiphene demonstrates that precise receptor-site selectivity can restore entire hormonal axes with minimal disruption. Retatrutide demonstrates that a single engineered polypeptide can coordinate metabolic signaling across three receptor families simultaneously.

Actionable next steps for researchers:

  1. Review GPER-specific literature to understand non-genomic estrogen signaling before designing peptide interaction studies.
  2. Use enclomiphene's HPG axis preservation model as a benchmark when evaluating upstream versus downstream peptide interventions.
  3. Consult Phase 2 retatrutide data for structural insights into multi-receptor polypeptide engineering.
  4. Explore the comprehensive peptide catalog to identify research compounds relevant to metabolic and hormonal pathway studies.
  5. Prioritize compounds with published quality testing data — see quality testing protocols — when designing rigorous endocrine research protocols.

The field is moving fast. Researchers who understand both the receptor-level architecture and the structural biology of the peptides involved will be best positioned to interpret emerging data as it arrives.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Peptides-and-Polypeptides-in-Endocrine-Research-Linking-Estrogen-Receptor-Signaling-to-Enclomiphene-and-GLP-3-Retatrutide-Models.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-23 13:05:442026-07-20 15:02:33Peptides and Polypeptides in Endocrine Research: Linking Estrogen Receptor Signaling to Enclomiphene and GLP-3 Retatrutide Models
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top