Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: serm research

Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments

Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments

October 7, 2026/0 Comments/in Uncategorized/by

Fewer than one in five commercial enclomiphene lots tested by independent analytical laboratories in recent years have carried full counterion confirmation alongside standard purity data, a gap that creates real problems when researchers try to compare results across batches or institutions. For anyone sourcing Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments, that single oversight can invalidate dosing calculations, skew receptor-binding data, and make batch-to-batch reproducibility impossible.

This guide moves beyond the basic base-versus-citrate comparison to give researchers a structured purchasing and verification checklist covering salt identity, assay method, residual solvents, counterion confirmation, and batch consistency.

Key Takeaways

  • Enclomiphene is supplied as either the free base or the citrate salt; the two forms carry different molecular weights, and failing to apply the correct salt factor corrupts dosing math in hormone-model experiments.
  • A complete Certificate of Analysis (COA) for research-grade material should include HPLC purity, NMR salt identity, ESI-MS confirmation, residual solvent data (GC headspace), and water content.
  • Counterion confirmation via NMR or ion chromatography is the most commonly missing data point in commercial COAs as of 2026.
  • Batch consistency checks, comparing COA values across at least two consecutive lots, are essential before committing to a long experimental series.
  • Enclomiphene is classified as a research-use-only compound in most jurisdictions; it is not approved for human use outside specific regulatory pathways.

Understanding the Two Chemical Forms: Base and Citrate

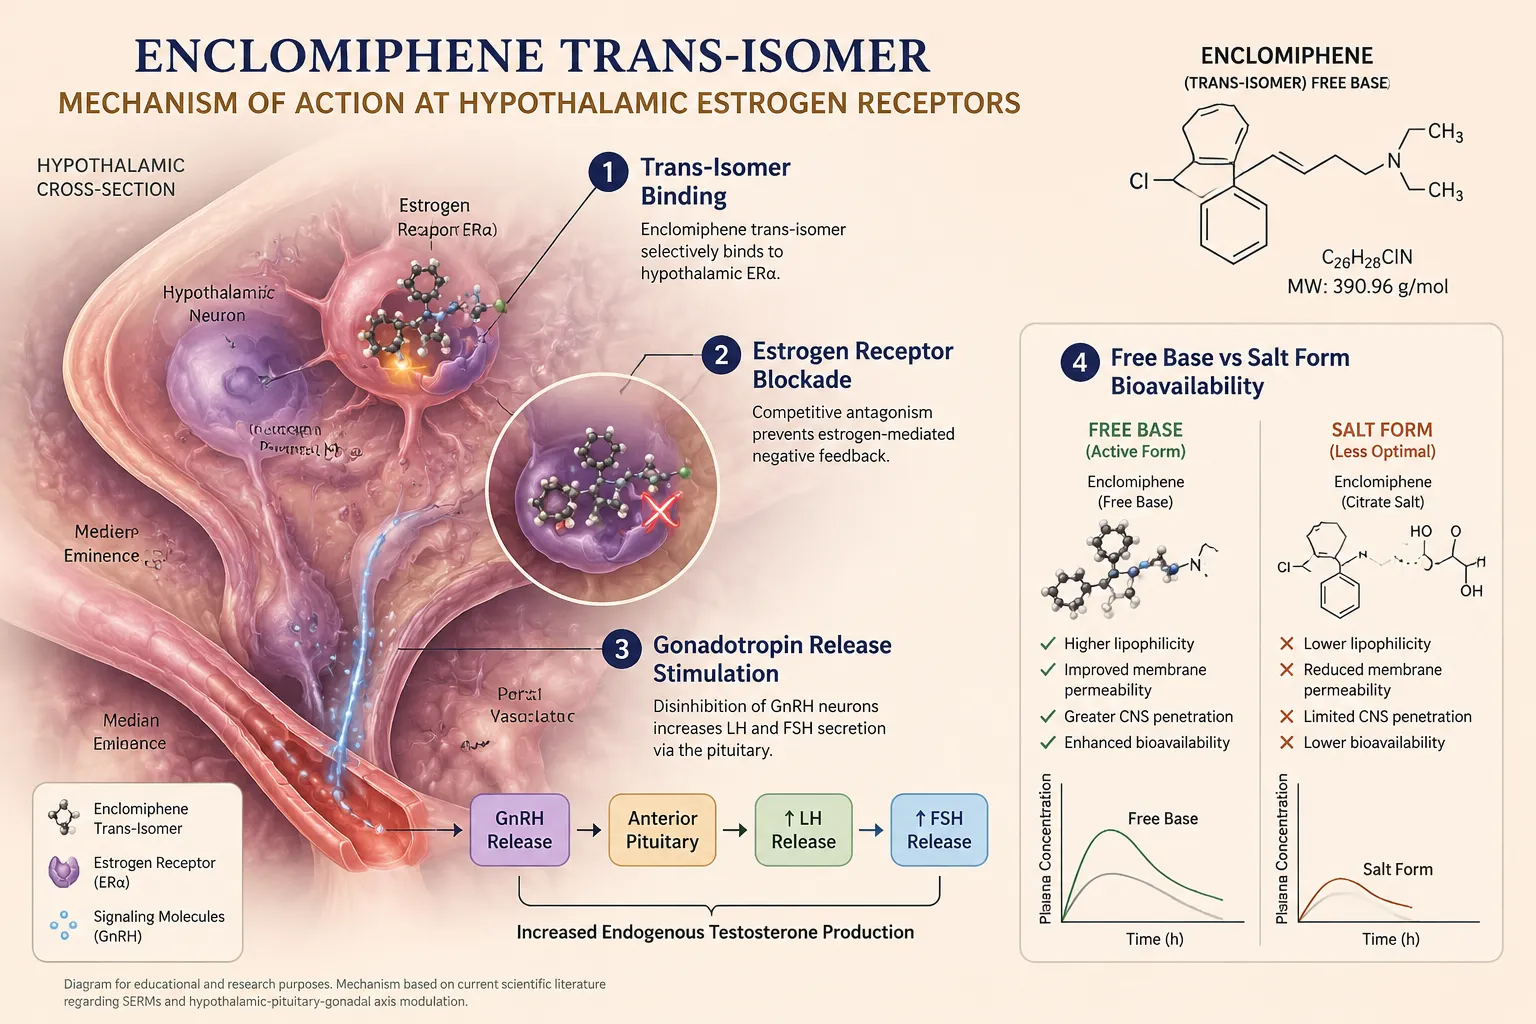
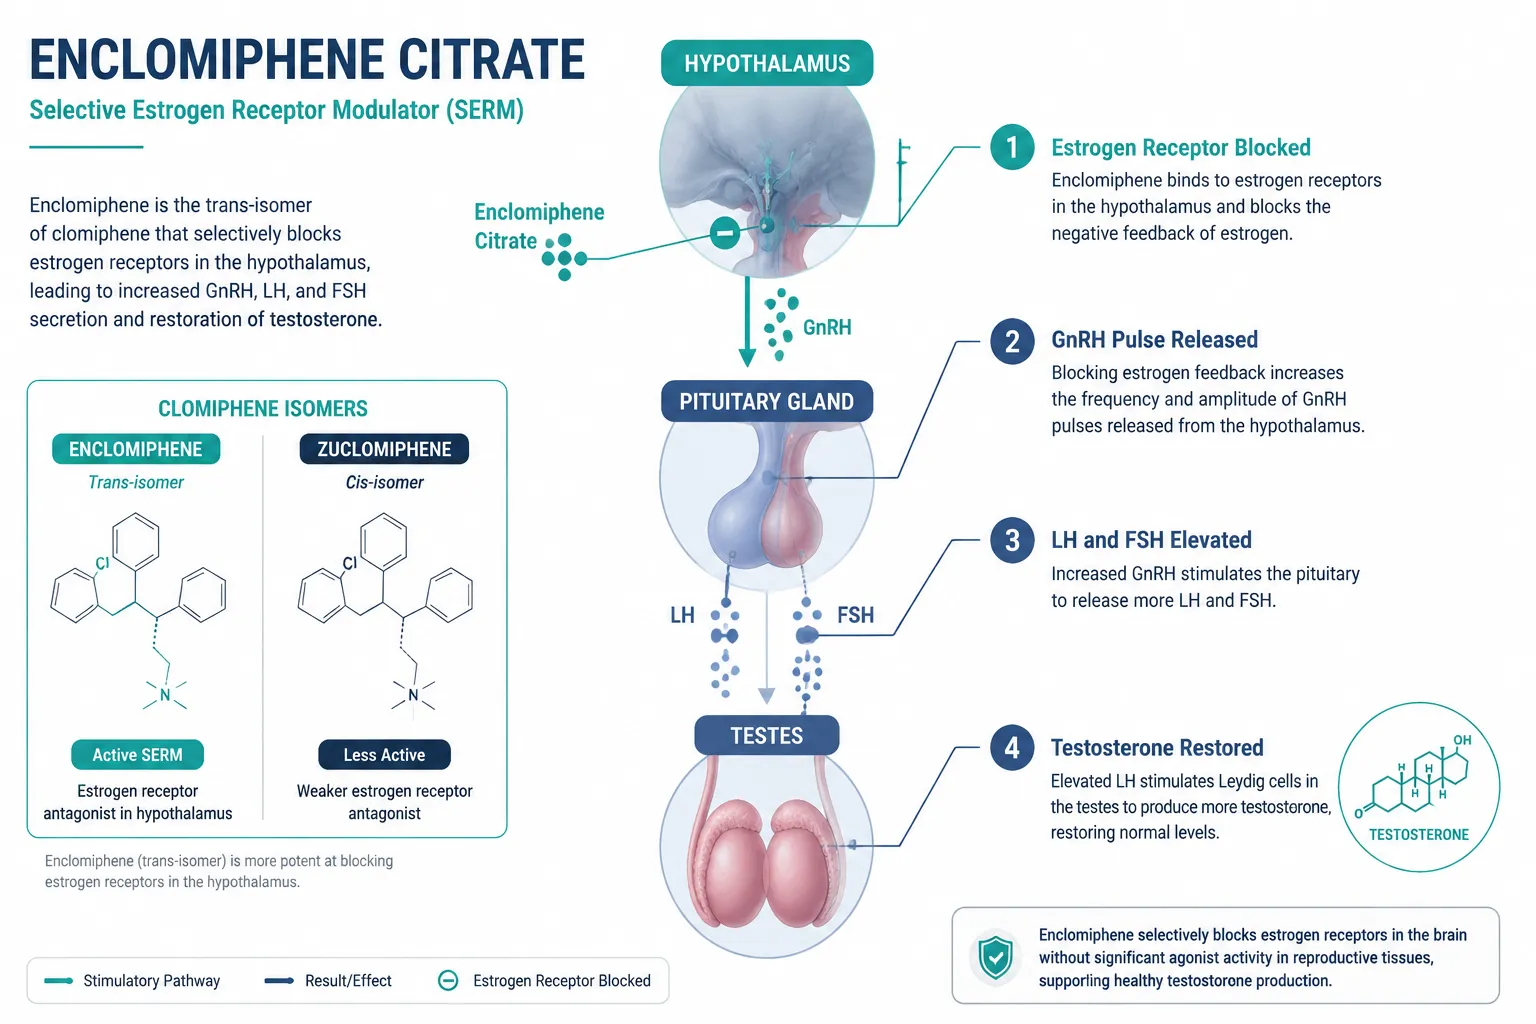
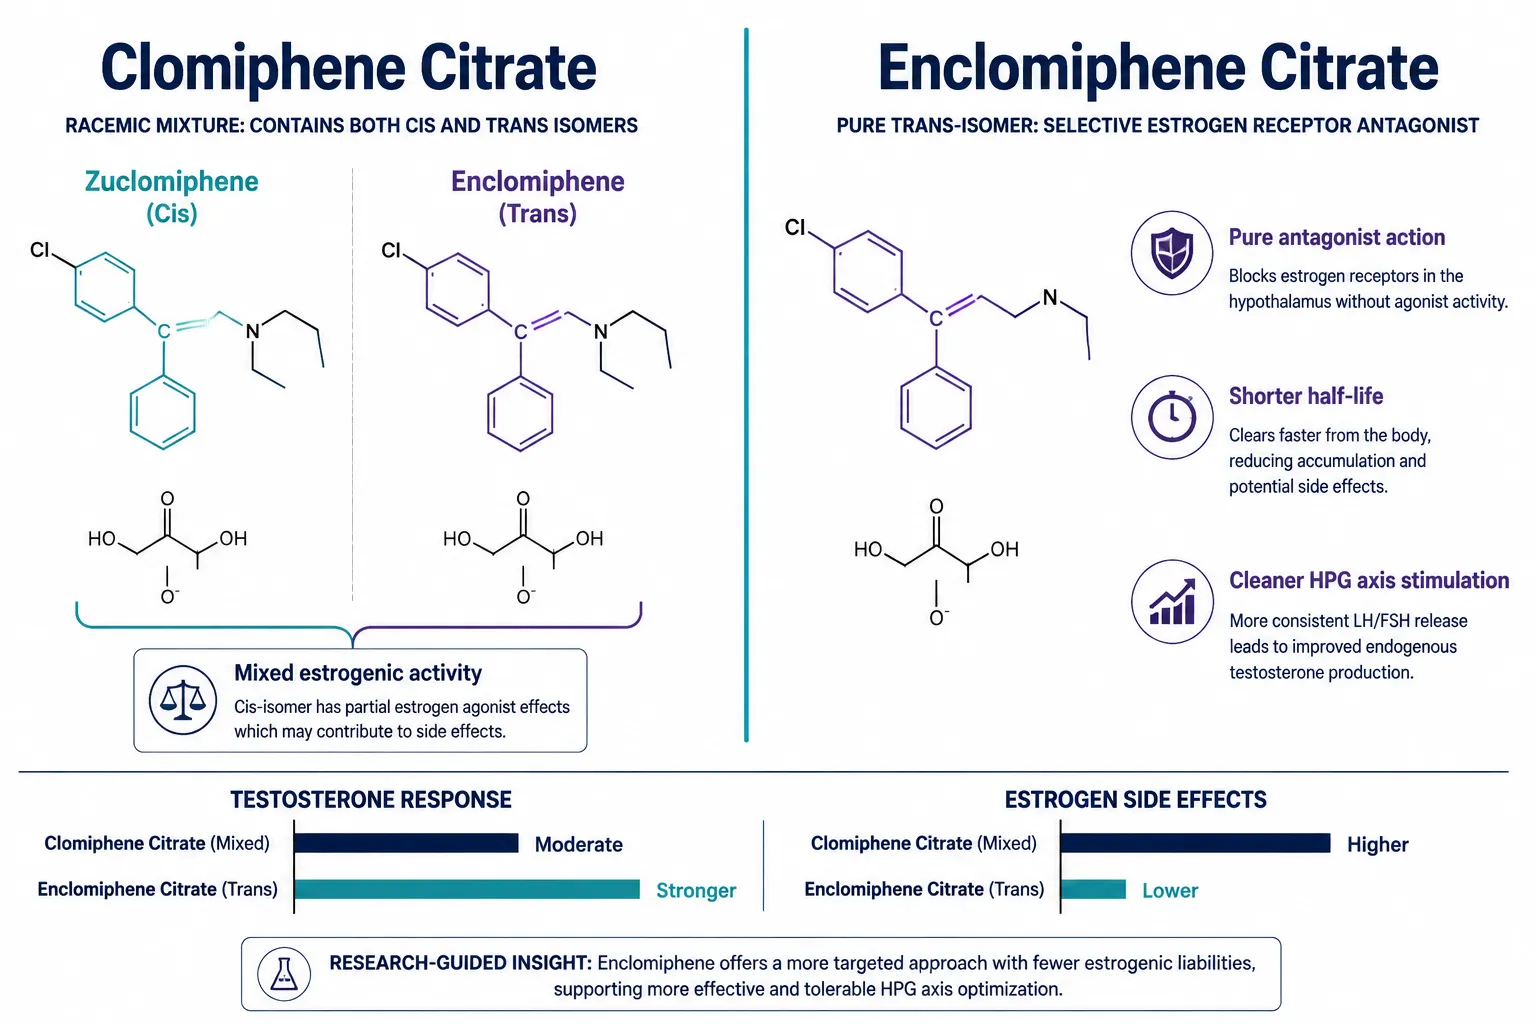
Enclomiphene is the trans-isomer of clomiphene, a selective estrogen receptor modulator (serm) that acts at hypothalamic estrogen receptors to reduce negative feedback on gonadotropin-releasing hormone. It reaches the market in two primary salt forms, and the distinction matters far more than many procurement workflows acknowledge.
Understanding the Two Chemical Forms: Base and Citrate

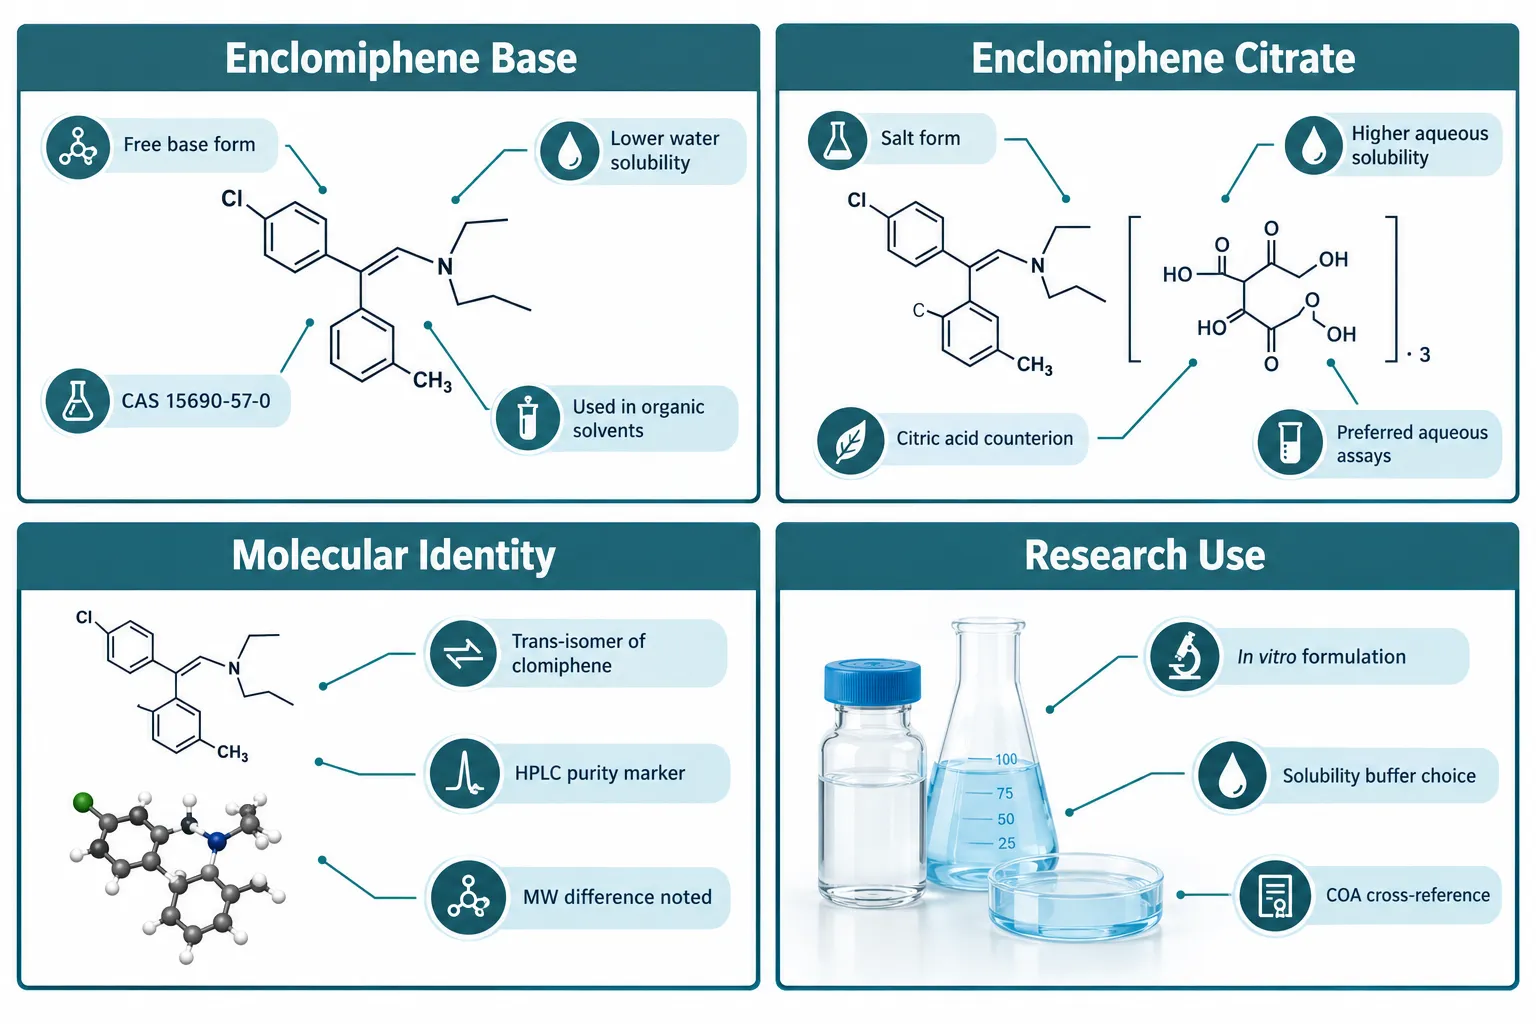
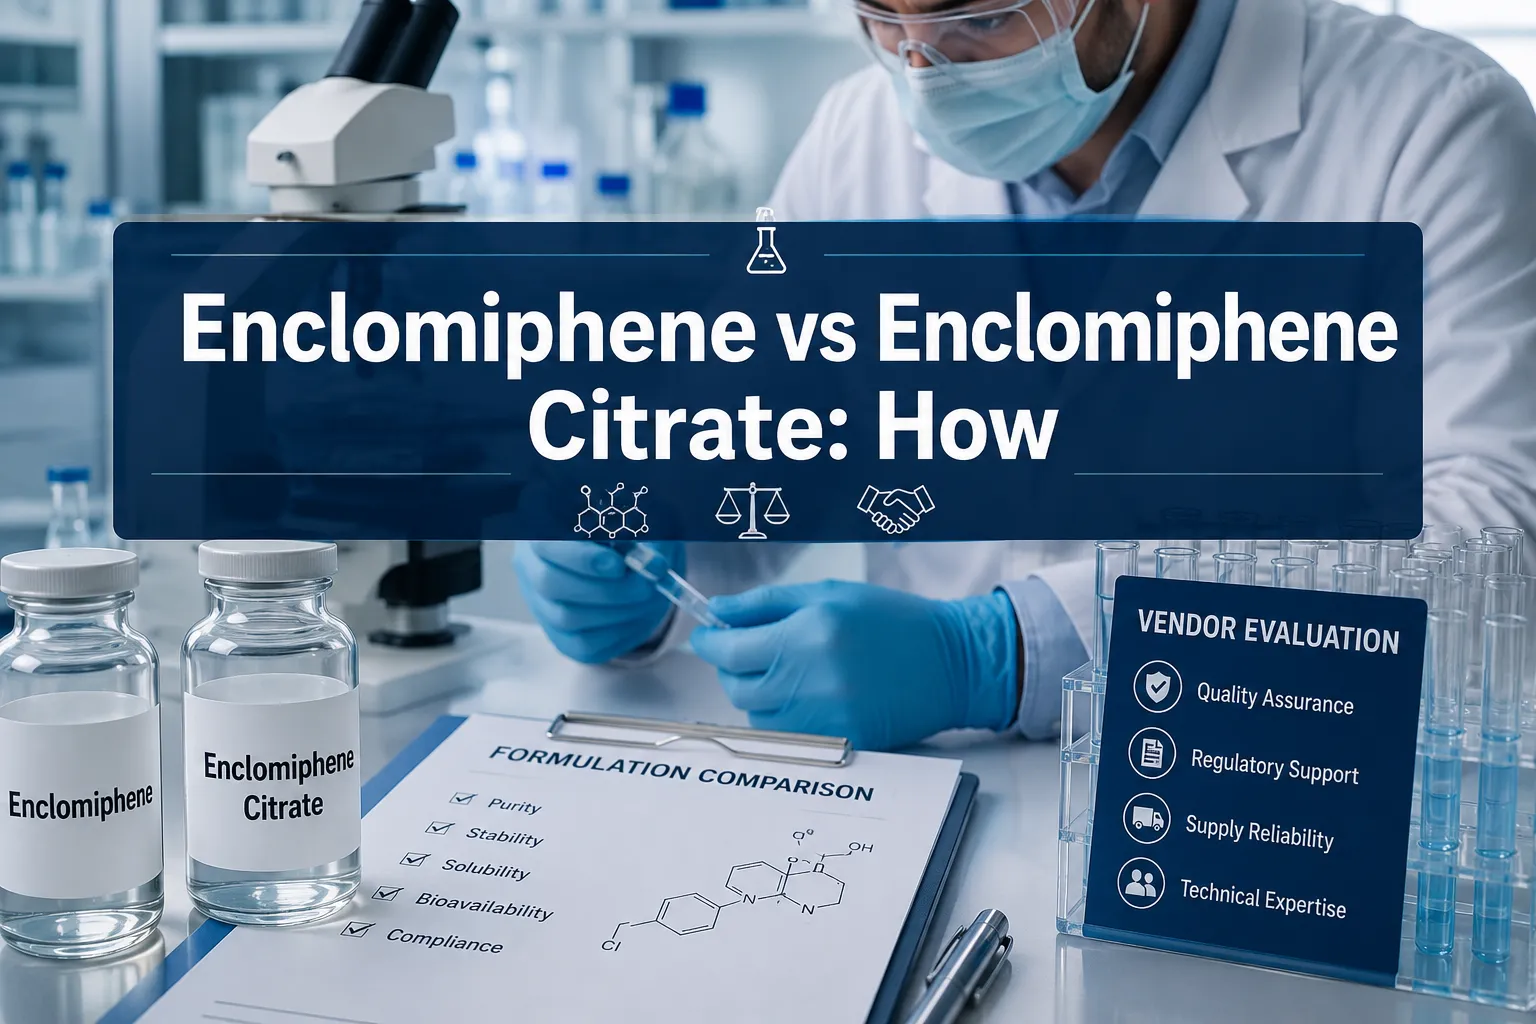
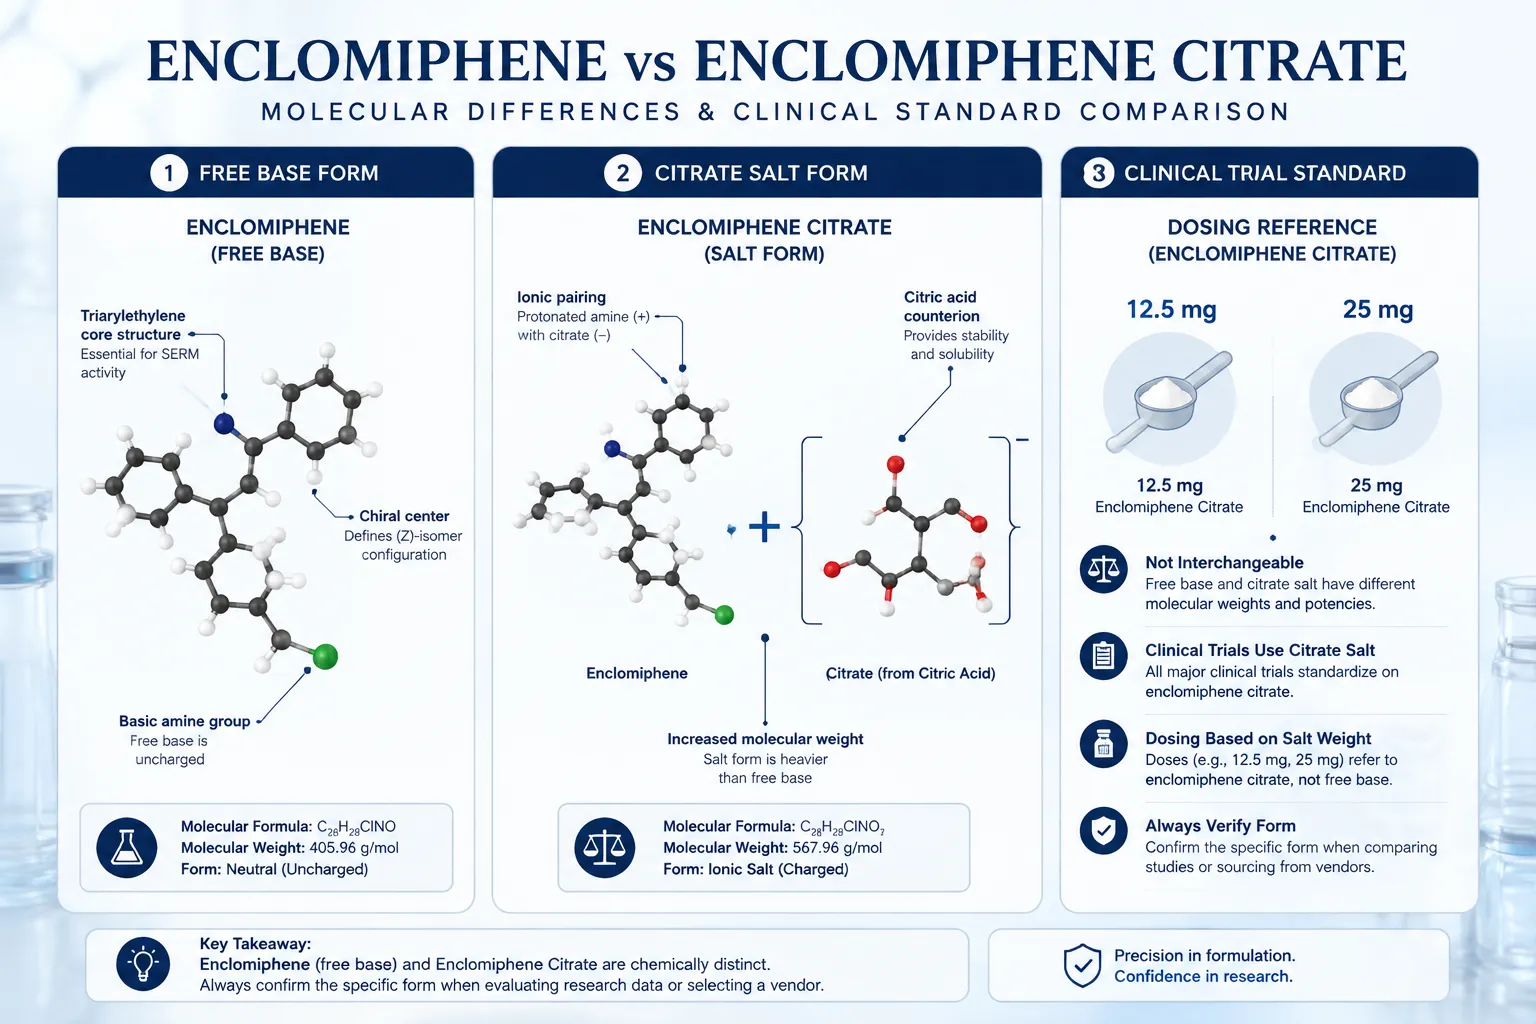
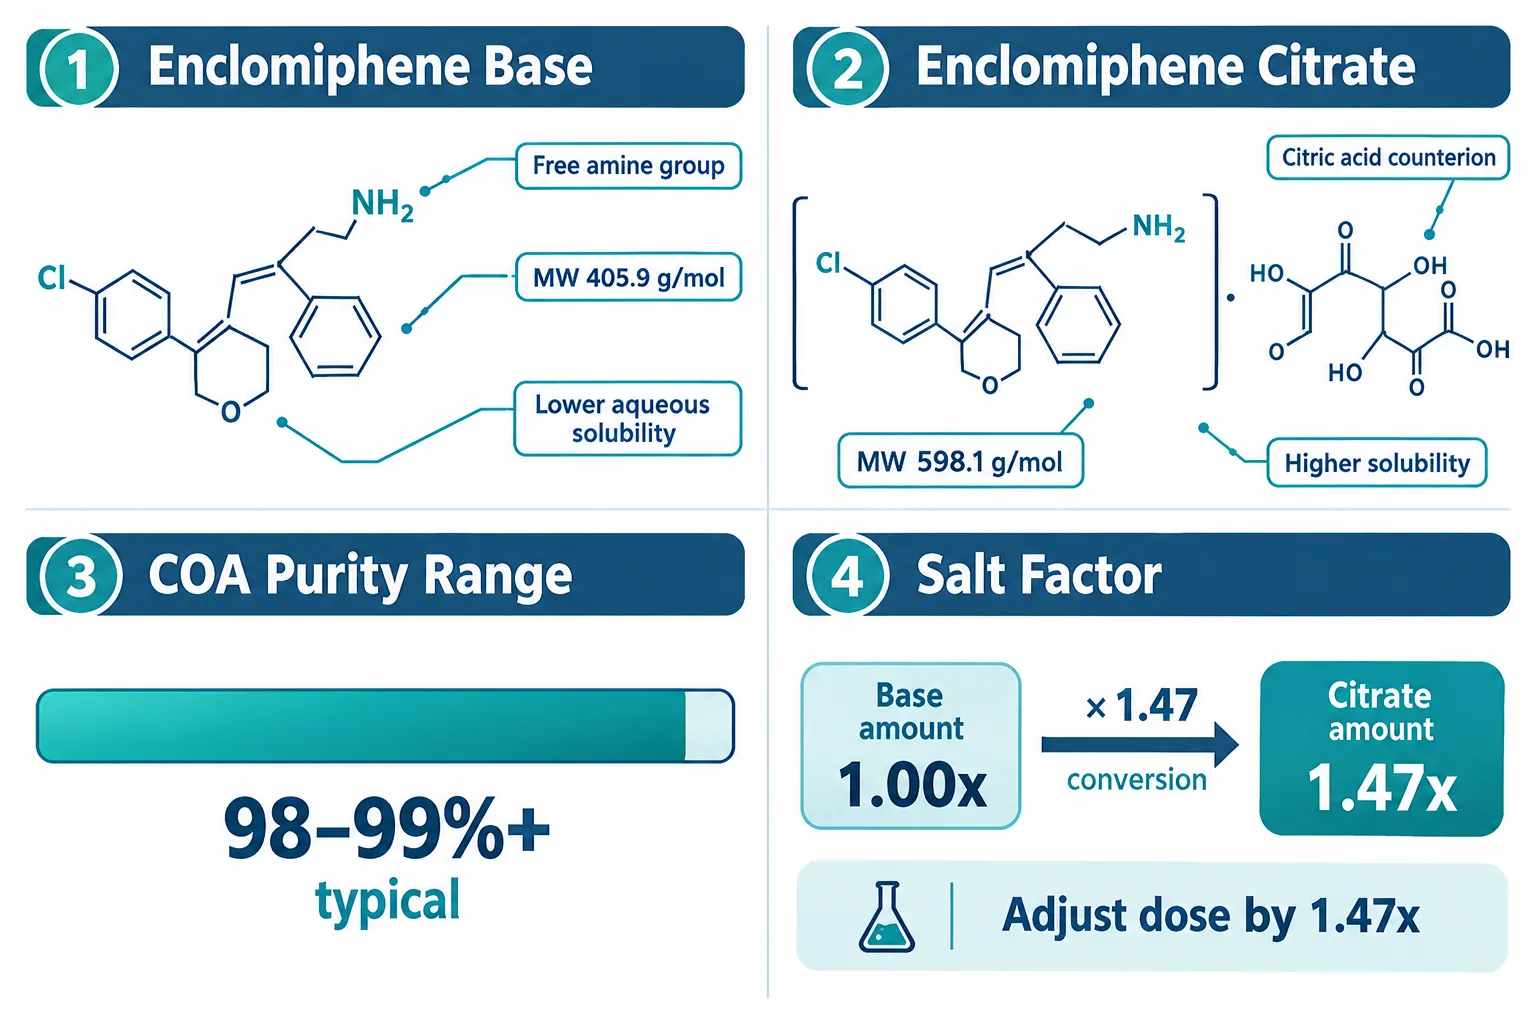
Enclomiphene free base carries a molecular weight of approximately 405.9 g/mol. It is less soluble in aqueous buffers, which makes it better suited to organic-solvent stock preparations (DMSO, ethanol) commonly used in cell-based assays. Enclomiphene citrate pairs the active molecule with citric acid as a counterion, raising the molecular weight to roughly 598.1 g/mol. The citrate form dissolves more readily in water, which is advantageous for in vitro hormone-model systems that require aqueous dosing vehicles.

The practical consequence: a researcher who assumes citrate when the material is actually the free base will underdose by approximately 32% relative to the active moiety. The conversion factor, roughly 1.47, must be applied whenever switching between forms or when a supplier's labeling is ambiguous.

Quick reference: key differences

Property Free Base Citrate Salt
Molecular weight ~405.9 g/mol ~598.1 g/mol
Aqueous solubility Low Moderate, high
Preferred vehicle DMSO / ethanol Aqueous buffer
Salt factor vs base 1.00 ~1.47
Counterion None Citric acid

Researchers building hormone-model systems, particularly hypothalamic-pituitary-gonadal (HPG) axis simulations, should document the chosen form in every experimental protocol. This is the same level of rigor applied when sourcing other structurally complex research agents; see the discussion of structural identity documentation in this overview of peptides 101 for research-use only buyers.


The Analytical Identity Checklist for Enclomiphene Research Materials

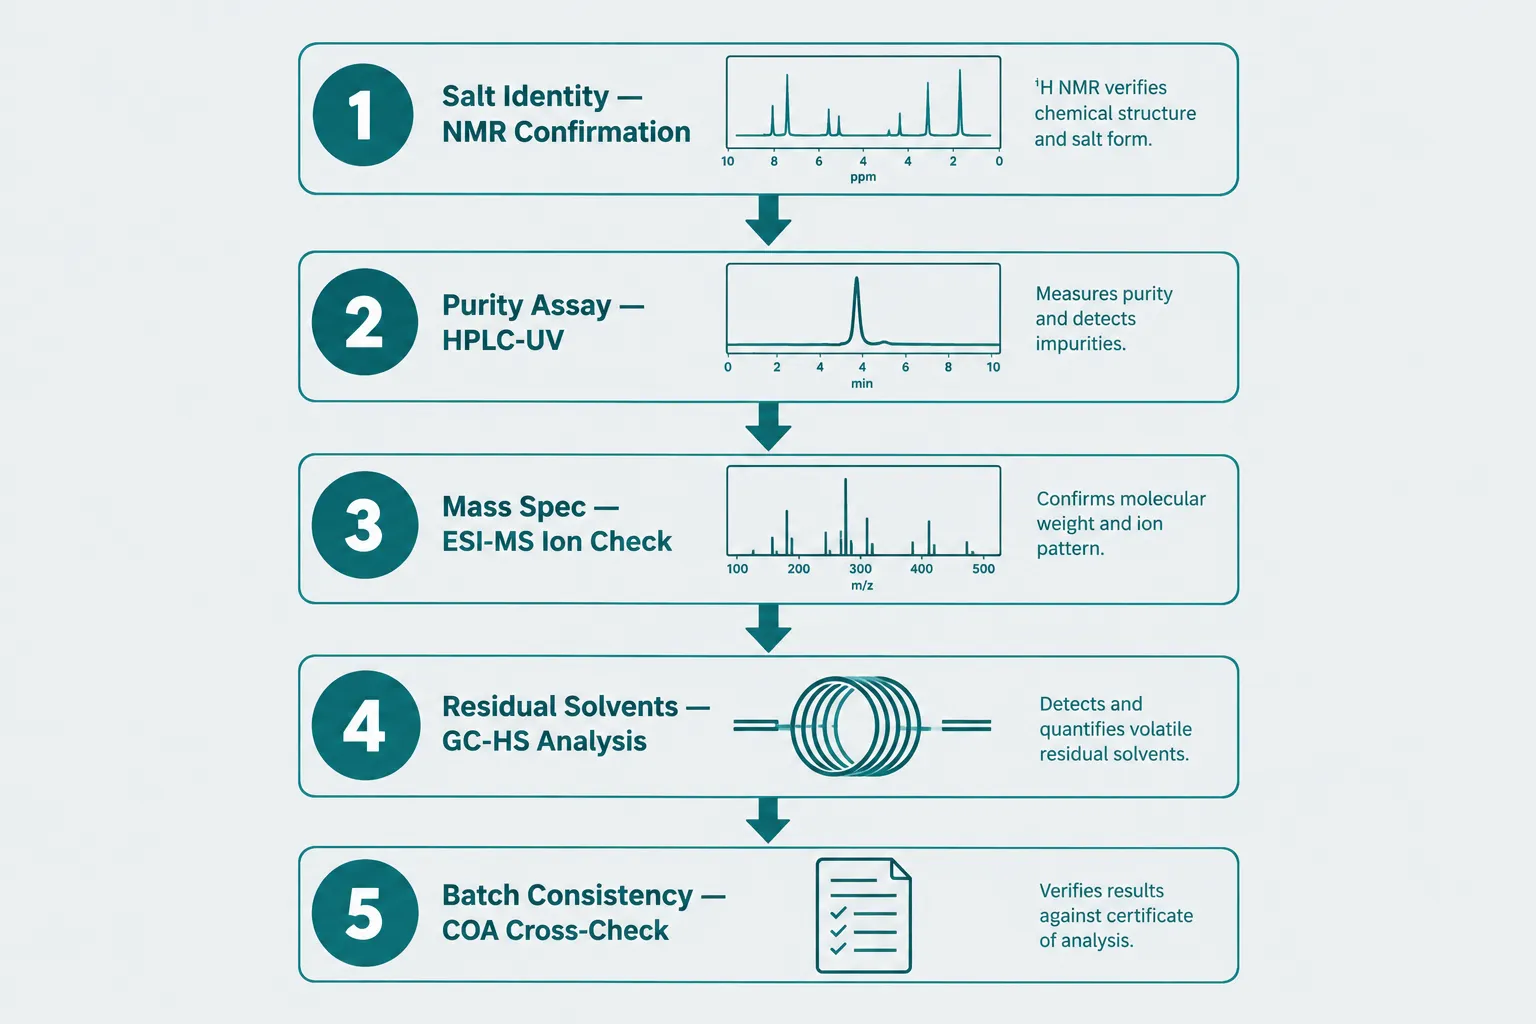
The core of responsible sourcing for Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments is a structured verification checklist applied to every lot before it enters an experiment. The following five-point framework covers the most critical analytical dimensions.
The Analytical Identity Checklist for Enclomiphene Research Materials

1. Salt Identity via NMR

Proton NMR (1H-NMR) is the gold-standard method for confirming whether a lot is the free base or a specific salt form. For the citrate, characteristic citric acid proton signals appear in the 2.5-2.8 ppm region. A COA that reports only HPLC purity without NMR data cannot confirm salt identity. Suppliers who provide NMR spectra as part of their documentation package should be prioritized.

2. Purity Assay via HPLC-UV

High-performance liquid chromatography with UV detection (typically at 254 nm) remains the standard purity assay. Research-grade material in 2026 is expected to meet 98% or higher purity by HPLC. The COA should specify the column type, mobile phase, and integration method. A single broad purity figure without chromatographic conditions is insufficient for experimental validation.

3. Mass Spectrometry Confirmation (ESI-MS)

Electrospray ionization mass spectrometry (ESI-MS) provides molecular ion confirmation independent of chromatographic separation. For enclomiphene free base, the expected [M+H]+ ion appears at m/z 406.2; for the citrate, the spectrum should show both the enclomiphene cation and the citrate anion. ESI-MS data on a COA rules out structural analogs and degradation products that can co-elute on HPLC.

4. Residual Solvents via GC Headspace

Synthesis and recrystallization of enclomiphene typically involves chlorinated solvents or alcohols. ICH Q3C residual solvent limits apply to pharmaceutical-grade material, and research-grade suppliers increasingly adopt these thresholds as a quality benchmark. Gas chromatography headspace (GC-HS) analysis should be requested for any lot used in cell-viability or receptor-binding assays where solvent contamination could confound results.

5. Counterion Confirmation via Ion Chromatography

This is the most commonly absent data point. Ion chromatography (IC) or capillary electrophoresis can quantify the citrate counterion directly, confirming the correct stoichiometry of the salt. Without it, a lot labeled "citrate" may be a partial salt or a mixed form. Batch-to-batch counterion ratio variation is a known source of irreproducibility in serm research.

Checklist summary:

  • NMR spectrum confirming salt form
  • HPLC-UV purity (98%+ with stated conditions)
  • ESI-MS molecular ion confirmation
  • GC-HS residual solvent panel
  • IC or CE counterion quantification
  • Karl Fischer water content (relevant for hygroscopic citrate lots)

Applying Verified Materials in Hormone-Model Experiments

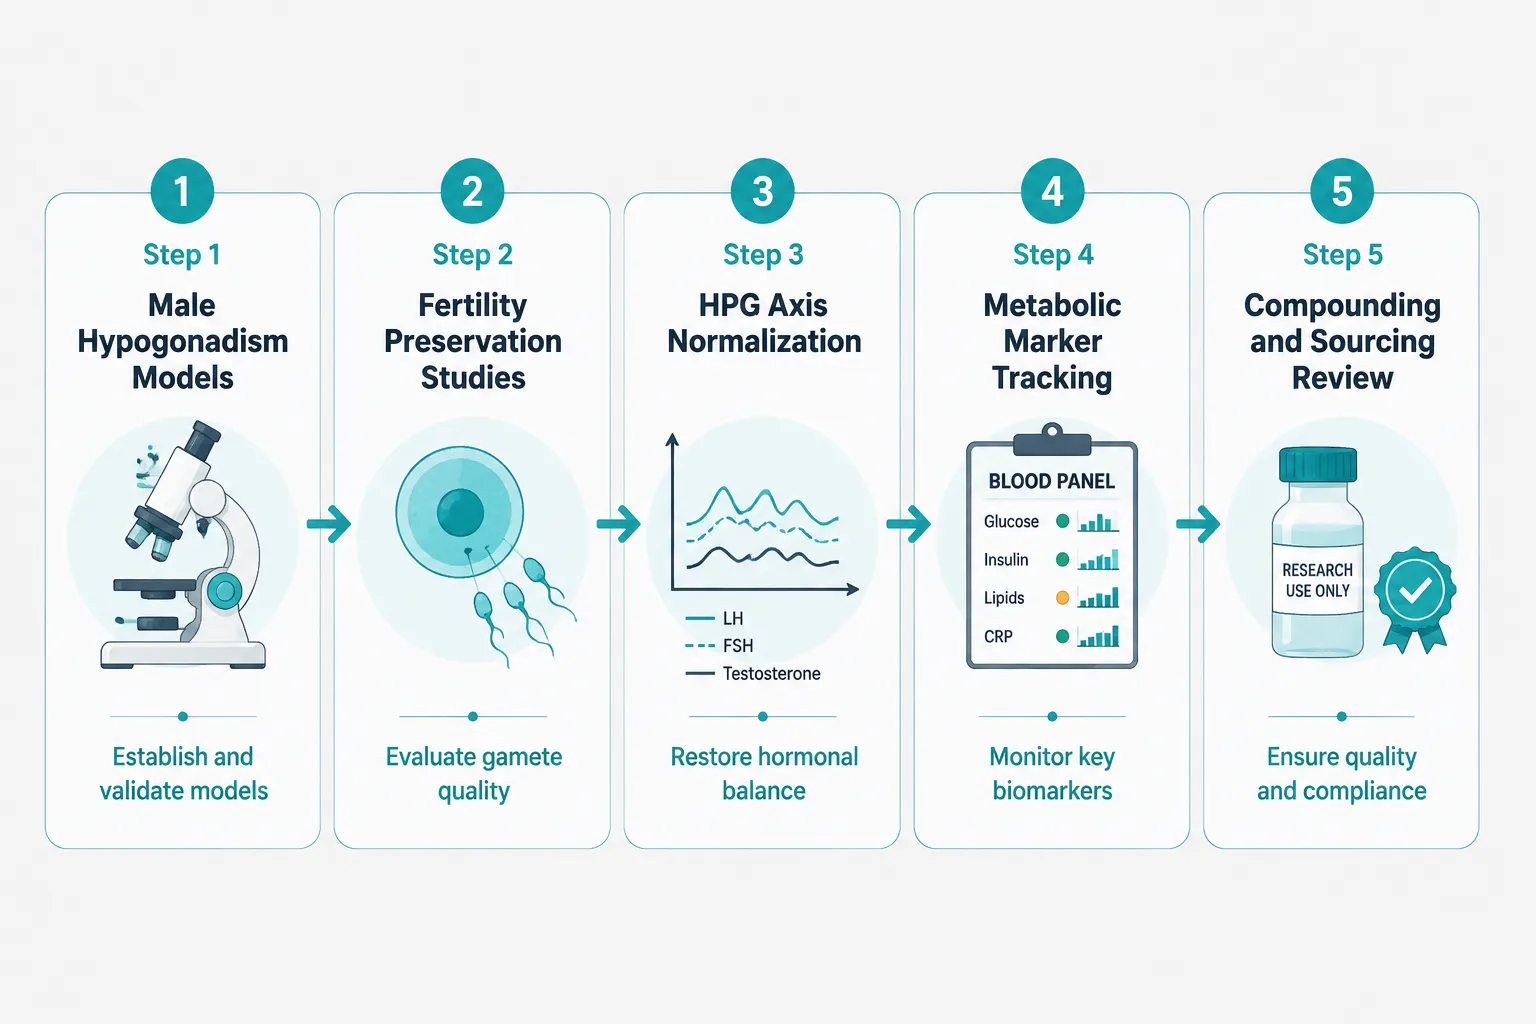
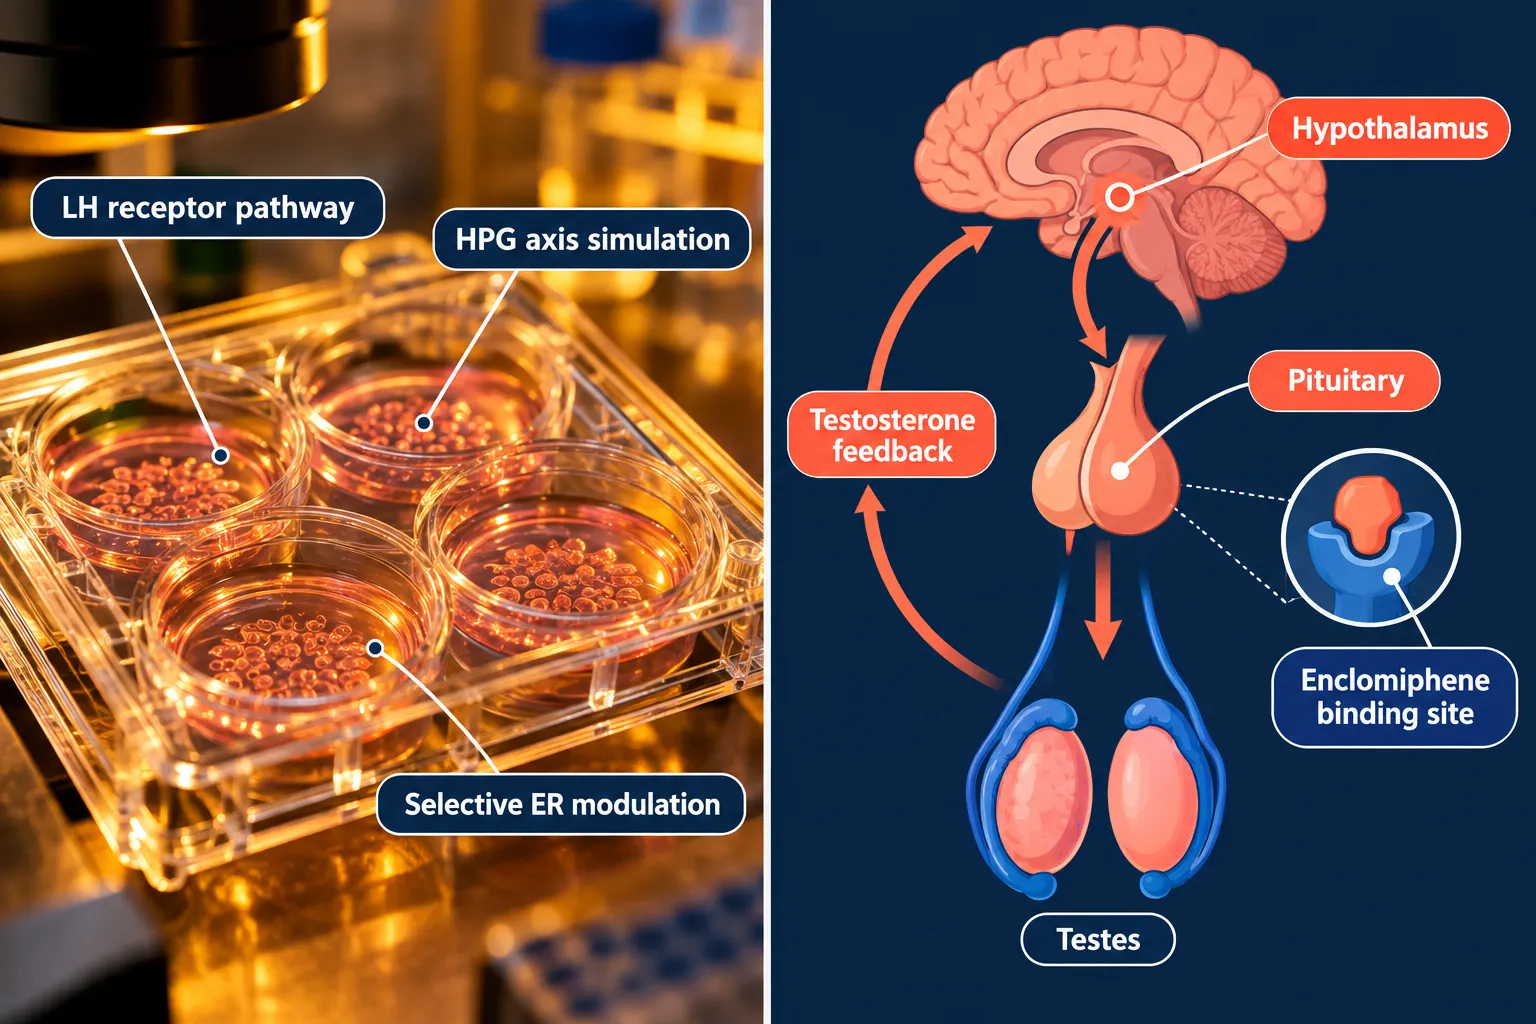
Once analytical identity is confirmed, the experimental design for HPG-axis hormone models can proceed with confidence. Enclomiphene's mechanism centers on competitive antagonism at hypothalamic estrogen receptors, which reduces estrogenic negative feedback and elevates luteinizing hormone (LH) and follicle-stimulating hormone (FSH) output. This makes it a useful tool in cell-based and ex vivo models studying gonadotropin regulation, male hypogonadism mechanisms, and fertility signaling.
Applying Verified Materials in Hormone-Model Experiments

For researchers working with aqueous dosing systems, the citrate form is generally preferred due to its superior solubility. For lipid-based or organic-vehicle assay systems, the free base dissolves more cleanly. In either case, stock solutions should be prepared fresh or stored under inert gas at -20°C to prevent oxidative degradation of the stilbene backbone.

Batch consistency across a multi-experiment series requires comparing COA values, purity, water content, and counterion ratio, across at least two consecutive lots before committing. A purity drop of even 1-2% between lots can translate to meaningful receptor-occupancy differences at low nanomolar concentrations typical of serm experiments.

The approach mirrors best practices seen in other research-grade compound categories. For example, the purity evaluation standards applied when sourcing research-grade Glow Blend Peptide materials follow the same logic: identity first, purity second, batch consistency third.

Researchers interested in broader hormone-axis modeling may also find value in reviewing growth hormone secretagogue mechanisms, such as the detailed pharmacokinetic profile covered in this CJC-1295 with and without DAC mechanism comparison, as multi-axis hormone models increasingly combine serm and GH-pathway tools.

For procurement teams evaluating supplier quality programs, the standards applied to wholesale peptides for sale at reputable suppliers, including third-party COA availability and batch traceability, provide a useful quality benchmark applicable to small-molecule research materials like enclomiphene as well.

"The counterion is not a footnote, it is half the molecule. Treating salt identity as an afterthought is one of the most preventable sources of irreproducibility in serm research."

As of mid-2026, regulatory positioning for enclomiphene remains research-use only in most jurisdictions outside specific approved clinical pathways. Researchers should confirm local regulatory status before procurement and ensure all use is confined to in vitro or appropriately approved in vivo model systems.


Conclusion

Sourcing Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments responsibly requires more than checking a purity percentage. The five-point analytical checklist, NMR salt identity, HPLC-UV purity, ESI-MS molecular confirmation, GC-HS residual solvents, and IC counterion quantification, gives research teams the data needed to dose accurately, compare results across batches, and publish reproducible findings.

Actionable next steps for research teams in 2026:

  1. Request full COA documentation including NMR and ESI-MS before approving any new lot.
  2. Apply the 1.47 salt factor correction whenever switching between base and citrate forms.
  3. Implement a batch-consistency log comparing at least two consecutive lot COAs before starting a new experimental series.
  4. Specify the dosing vehicle (aqueous vs. organic) in the protocol and select the appropriate salt form accordingly.
  5. Confirm the regulatory classification of enclomiphene in your jurisdiction before procurement.

Analytical rigor at the purchasing stage is the cheapest insurance a research program can buy.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/enclomiphene-research-materials-base-citrate-and-analytical-identity-checks-for.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-07 13:04:082026-10-07 13:04:08Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments
Enclomiphene Research Materials: Enclomiphene Base vs Citrate for Identity, Solubility, and COA Review

Enclomiphene Research Materials: Enclomiphene Base vs Citrate for Identity, Solubility, and COA Review

September 28, 2026/0 Comments/in Uncategorized/by

Fewer than a handful of small-molecule research compounds generate as much procurement confusion as enclomiphene, largely because researchers routinely receive materials labeled under two chemically distinct forms without clear guidance on how that distinction affects their assay design. Selecting the correct form from the outset, and then verifying it through proper documentation, is not a minor administrative step. For anyone sourcing enclomiphene research materials: enclomiphene base vs citrate for identity, solubility, and COA review, understanding the chemical and analytical differences between these two forms is the foundation of reproducible, well-documented laboratory work.

Key Takeaways

  • Enclomiphene base and enclomiphene citrate are chemically distinct forms with different molecular weights, solubility profiles, and documentation requirements.
  • Enclomiphene citrate offers meaningfully higher aqueous solubility, making it preferable for buffer-based in vitro assays.
  • Enclomiphene base is better suited to organic solvent systems such as DMSO or ethanol.
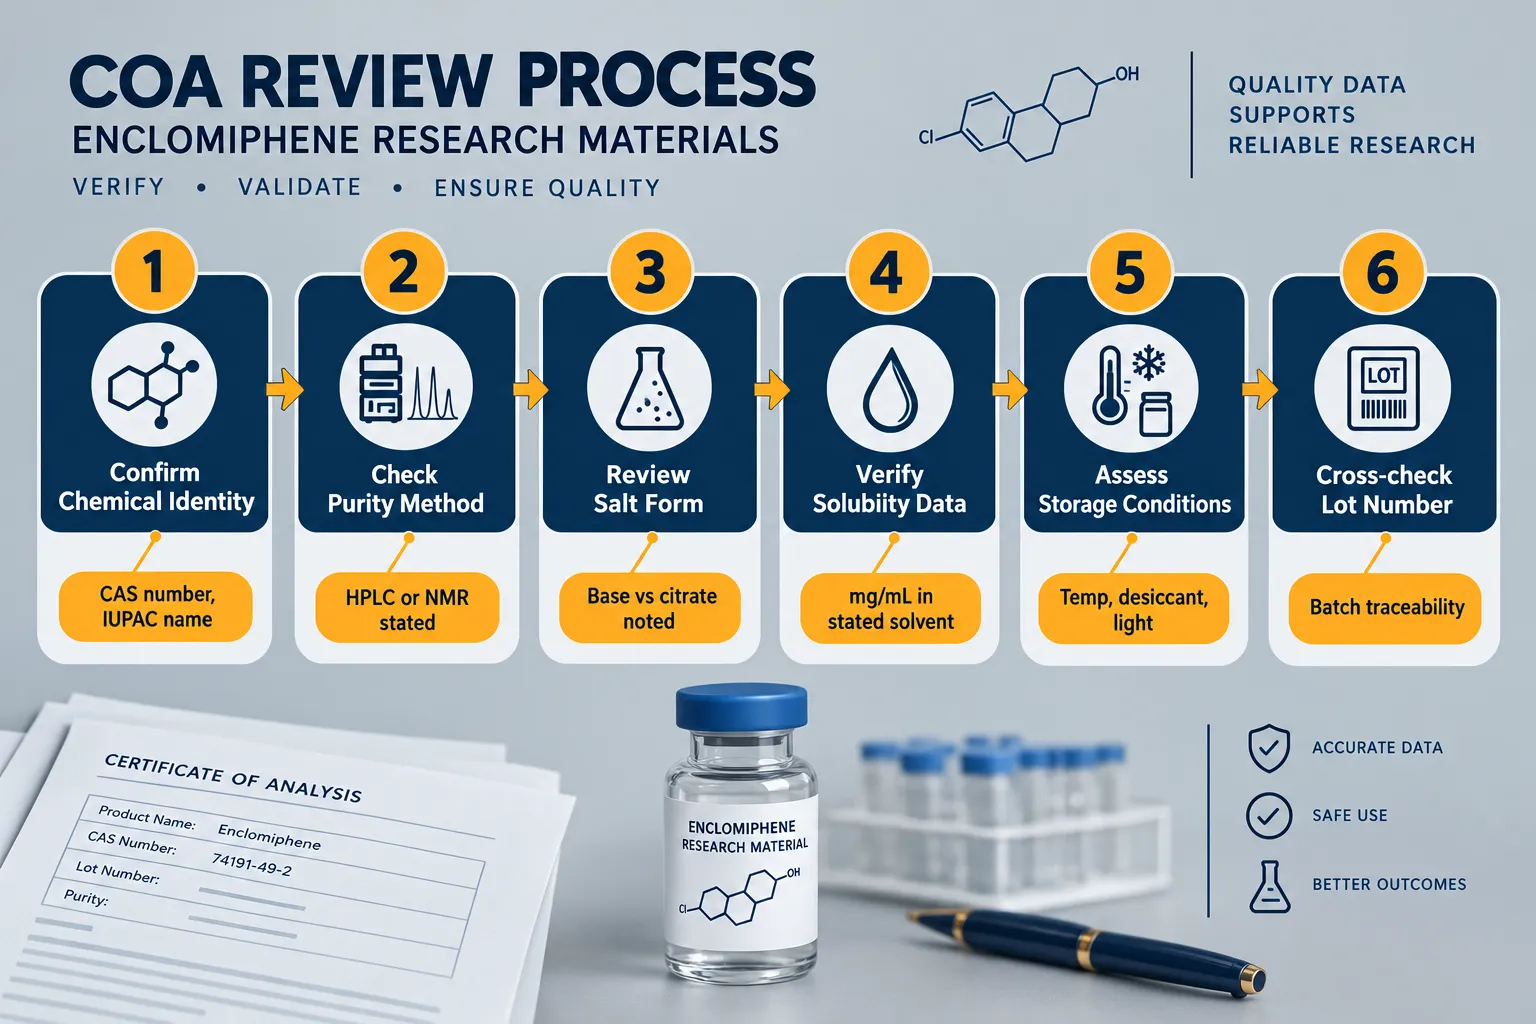
  • A high-quality Certificate of Analysis must explicitly state the salt form, CAS number, purity method, and solubility data, not just a percentage purity figure.
  • As of 2026, enclomiphene holds no FDA-approved indication in any form; all procurement and use remains within a research-only context.

Chemical Identity: What Separates Enclomiphene Base from Its Citrate Salt

Chemical Identity: What Separates Enclomiphene Base from Its Citrate Salt

Enclomiphene is the trans-isomer of clomiphene, a selective estrogen receptor modulator (serm) that has been studied for its effects on the hypothalamic-pituitary-gonadal axis. The base form (free base) carries CAS number 15690-57-0 and represents the compound in its uncharged, non-salt state. The citrate salt is formed when the base is combined with citric acid, producing a counterion pair that significantly alters the compound's physical and chemical behavior.

This distinction matters immediately at the procurement stage. A supplier listing "enclomiphene" without specifying salt form is providing incomplete information. Researchers should confirm:

  • Exact CAS number (base vs. citrate have different registry entries)
  • Molecular weight (the citrate salt is heavier due to the citric acid moiety)
  • IUPAC name or systematic name confirming the trans-configuration
  • Salt ratio (typically 1:1 for citrate salts, but this should be stated explicitly)

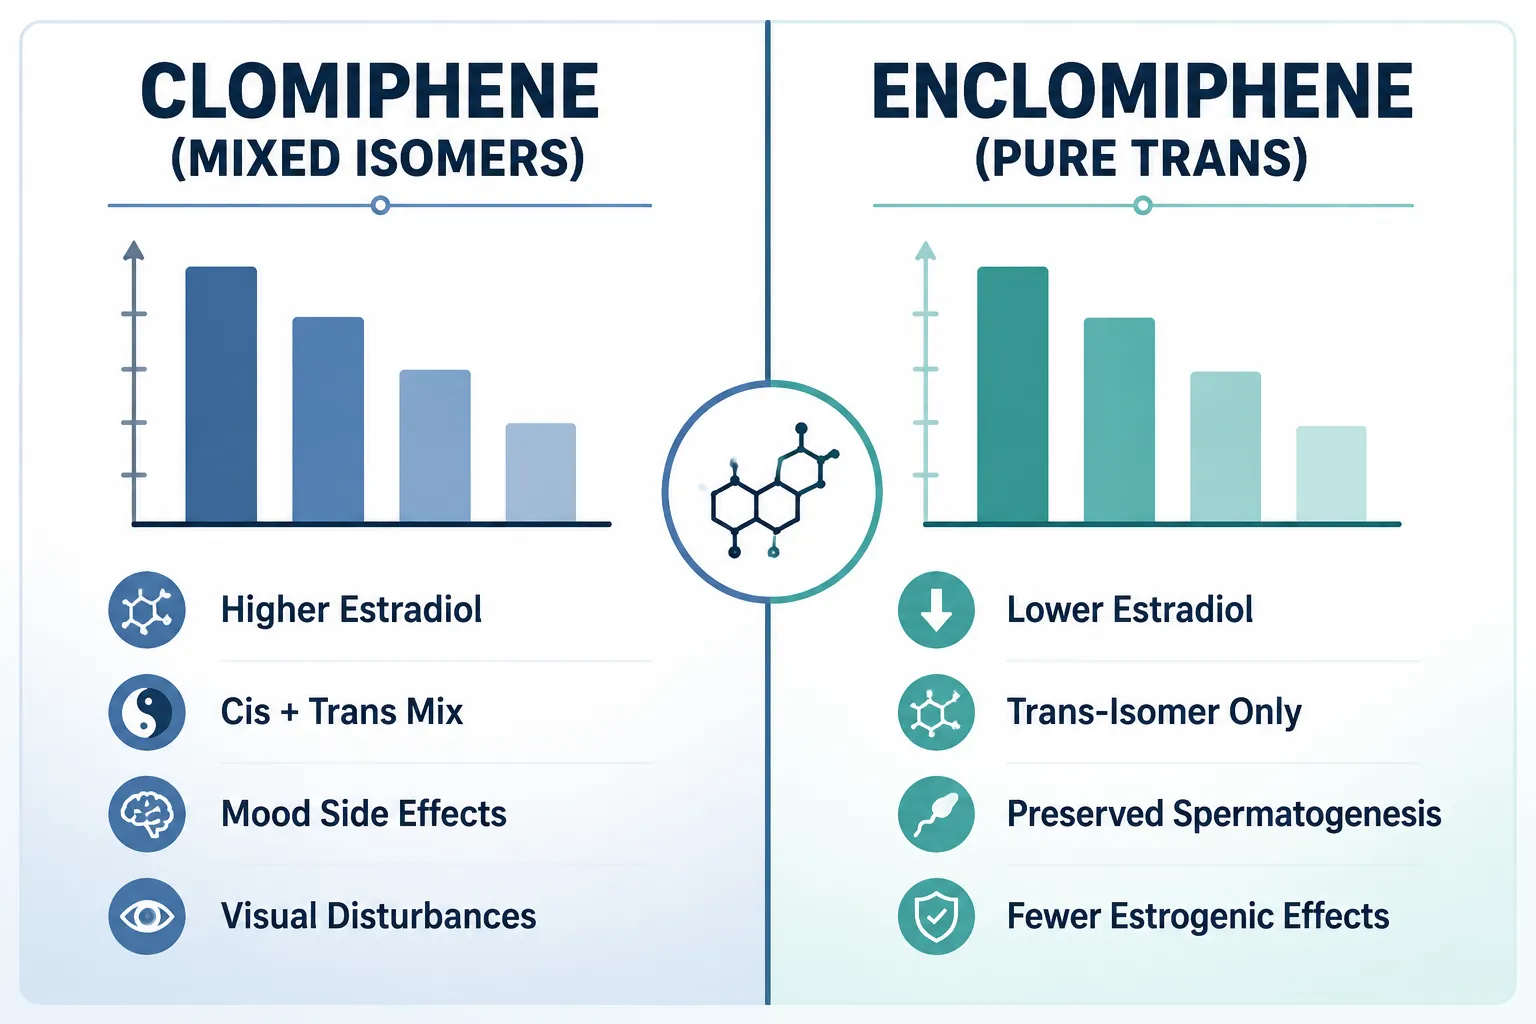
Clomiphene citrate, the racemic mixture containing both enclomiphene and zuclomiphene, has a long clinical history. Enclomiphene as an isolated isomer is a more refined research material, and its documentation standards should reflect that precision. Researchers comparing enclomiphene to other research-grade serms can find relevant context in the serm 10mg product documentation as a reference point for how salt-form labeling should appear on supplier listings.


Solubility Profiles: Matching the Form to the Assay

Solubility Profiles: Matching the Form to the Assay

Solubility is where the base-versus-citrate distinction has the most direct impact on experimental planning. The two forms behave very differently across common laboratory solvents.

Enclomiphene Base, Solubility Summary

Solvent Solubility
DMSO Moderate to good (~10-25 mg/mL typical)
Ethanol Moderate
Water Very low (practically insoluble)
Aqueous buffers Not suitable without co-solvent

Enclomiphene Citrate, Solubility Summary

Solvent Solubility
Water Measurably higher than base form
Aqueous buffers (pH 4-7) Acceptable for in vitro use
DMSO Also soluble
Ethanol Soluble

The citrate salt form improves aqueous solubility because the ionic character of the salt increases hydrophilicity. This is consistent with the broader pharmacology of clomiphene citrate, where the citrate counterion has historically been used precisely to improve handling in aqueous media. For researchers designing cell-based assays or receptor binding studies in aqueous buffer systems, enclomiphene citrate is the more practical choice. For organic solvent stock solutions intended for dilution into non-aqueous matrices, the base form is workable.

"Choosing the wrong salt form for an aqueous assay can introduce solubility artifacts that invalidate dose-response data, a problem that is entirely avoidable with upfront documentation review."

Researchers working with other peptides and small molecules that require careful solubility planning, such as those reviewing Bachem and reference standards for building robust peptide benchmarks, will recognize this as a standard quality-control consideration across compound classes.


COA Review: What a High-Quality Document Must Contain

COA Review: What a High-Quality Document Must Contain

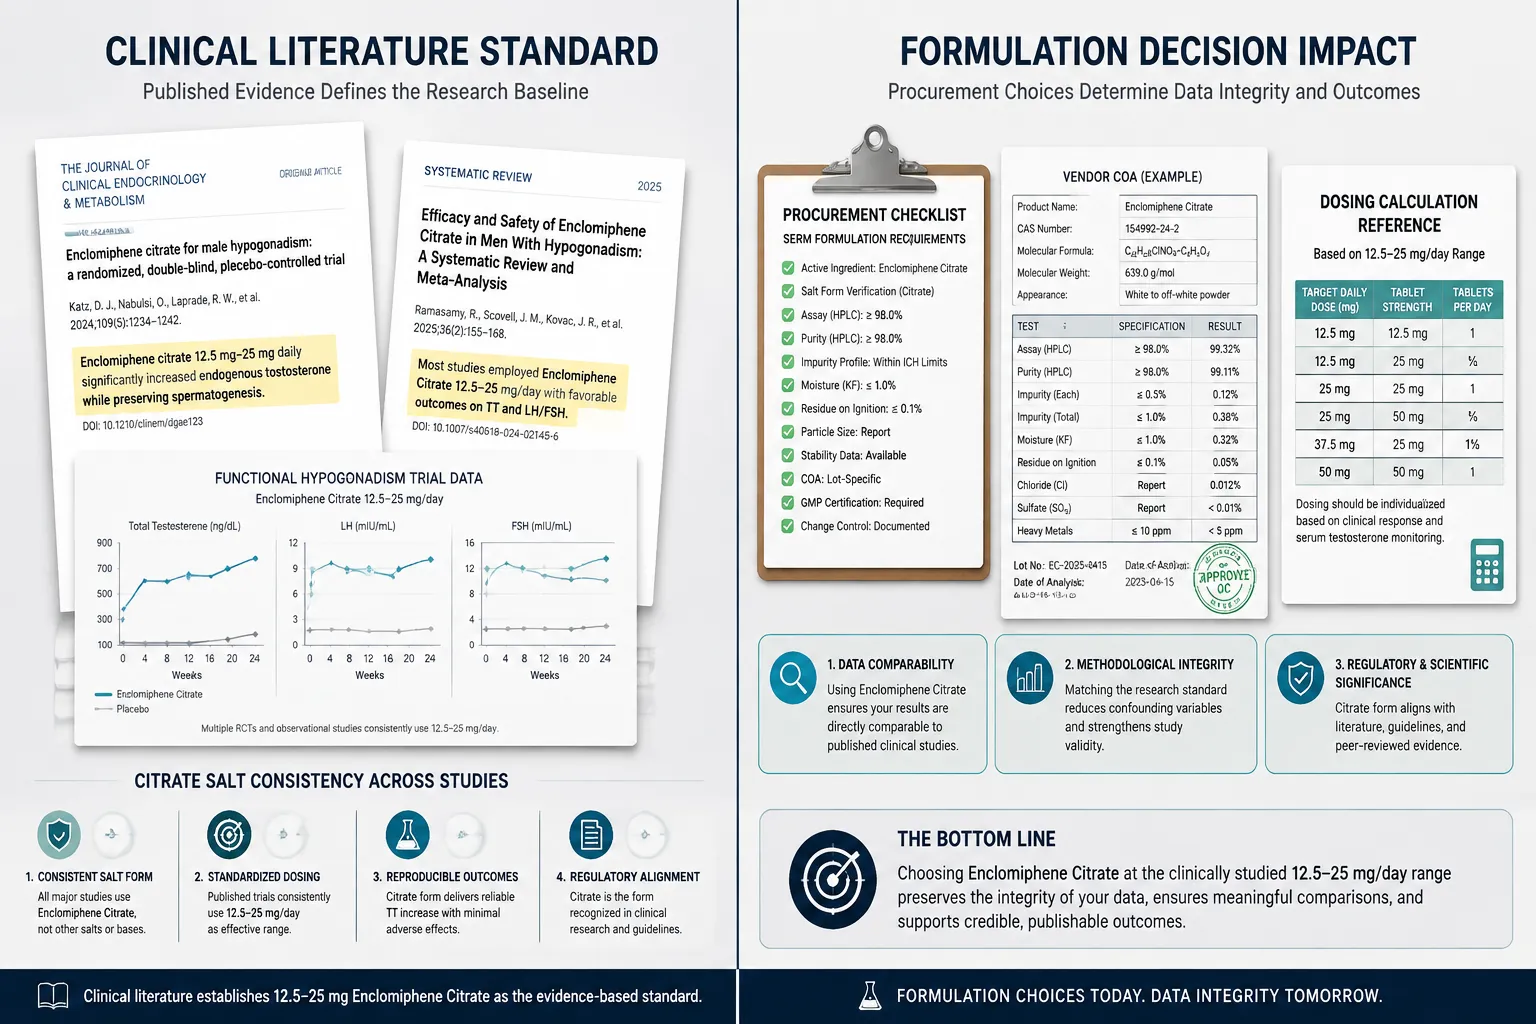
A Certificate of Analysis (COA) is not simply a purity number on a page. For enclomiphene research materials, whether base or citrate, a complete COA should contain the following elements, and researchers should decline materials where any of these are absent.

Required COA Elements for Enclomiphene Research Materials

  1. Chemical name and salt form, explicitly stating "enclomiphene citrate" or "enclomiphene free base," not just "enclomiphene"
  2. CAS number, matching the stated form
  3. Molecular formula and molecular weight, allowing the researcher to verify the correct form independently
  4. Purity method, HPLC is the standard; NMR is acceptable as a supplementary identity confirmation
  5. Purity result, expressed as area percentage from HPLC, with the method conditions (column type, mobile phase, wavelength) ideally referenced
  6. Isomeric confirmation, documentation that the material is the trans-isomer (enclomiphene), not the cis-isomer (zuclomiphene) or the racemate
  7. Solubility data, stated solvent, concentration, and whether the solution was clear or required sonication
  8. Lot or batch number, for traceability
  9. Storage conditions, temperature, desiccant requirement, light sensitivity
  10. Manufacturer or testing laboratory identity

As of 2026, enclomiphene citrate appears in some NDC (National Drug Code) listings, but this does not constitute FDA approval of any enclomiphene product. Researchers should not interpret an NDC listing as a regulatory clearance signal. All procurement of enclomiphene in any form remains strictly within research contexts, and COA documentation should be evaluated accordingly.

Researchers familiar with documentation standards for other well-characterized compounds, such as those reviewing SS-31 mechanism and research sourcing considerations, will find the same principles apply: supplier transparency, third-party testing, and explicit lot traceability are non-negotiable.


Formulation Strategies and Assay Planning Considerations

Knowing the form is only the first step. Translating that knowledge into a working formulation requires a few additional decisions.

For enclomiphene citrate in aqueous systems:

  • Prepare stock solutions in sterile water or phosphate-buffered saline
  • Confirm clarity visually and via UV absorbance baseline before use
  • Note that pH can affect solubility, acidic conditions (pH 4-5) generally favor dissolution

For enclomiphene base in organic solvent systems:

  • DMSO stocks at 10 mg/mL are a common starting point
  • Dilute into aqueous media at no more than 0.1% DMSO final concentration to avoid solvent cytotoxicity in cell assays
  • Sonication in a water bath (37°C, 15-30 minutes) can aid dissolution

Researchers sourcing other research-grade materials that require similar formulation planning, including those exploring IPA sermorelin stack research or reviewing tesa dosage considerations, will recognize that solvent compatibility and stock preparation protocols are just as important as compound identity.

For researchers also working with compounds in the aging support category, cross-referencing COA documentation practices across compound classes is a useful habit that strengthens overall laboratory quality standards.


Conclusion

Procuring enclomiphene research materials without first resolving the base-versus-citrate distinction is a preventable source of experimental error. The two forms differ in molecular weight, aqueous solubility, and the documentation that should accompany them. A COA that fails to specify salt form, purity method, or isomeric identity is insufficient for rigorous research use.

Actionable next steps for researchers in 2026:

  • Request full COA documentation before purchase, and verify that salt form and CAS number are explicitly stated
  • Match the form to the solvent system: citrate for aqueous assays, base for organic solvent stocks
  • Cross-check the stated molecular weight against published values for the specific form to catch mislabeling
  • Confirm isomeric purity (trans-enclomiphene vs. cis-zuclomiphene) through HPLC or NMR data on the COA
  • Treat any NDC listing as administrative, not as a regulatory approval signal

Rigorous identity verification and documentation review are the difference between reproducible data and ambiguous results. Applying these standards consistently, across enclomiphene and every other research compound in the laboratory, is the hallmark of credible, defensible research practice.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/enclomiphene-research-materials-enclomiphene-base-vs-citrate-for-identity-solubi.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-28 13:04:022026-09-28 13:04:02Enclomiphene Research Materials: Enclomiphene Base vs Citrate for Identity, Solubility, and COA Review
Enclomiphene Citrate vs Enclomiphene: Stability, Storage, and Research Handling

Enclomiphene Citrate vs Enclomiphene: Stability, Storage, and Research Handling

September 15, 2026/0 Comments/in Uncategorized/by

Most researchers who order enclomiphene for laboratory work assume the citrate salt and the free base are the same compound with a different label. That assumption can compromise data, shorten shelf life, and introduce variables that are difficult to trace back to the source material. Understanding the distinctions in Enclomiphene Citrate vs Enclomiphene: Stability, Storage, and Research Handling is not a minor technical footnote, it is foundational to reproducible science.

Key Takeaways

  • Enclomiphene citrate is a salt form of enclomiphene; the citrate counterion meaningfully changes solubility, crystalline stability, and handling requirements.
  • Research-grade powder in either form is significantly more stable than aqueous or organic solutions, which degrade faster under ambient conditions.
  • Both forms are sensitive to light, moisture, and heat; amber vials, desiccants, and cold storage are non-negotiable for long-term integrity.
  • Finished formulations such as capsules and liquid suspensions show acceptable stability at or below 25 °C when properly packaged.
  • Vendor quality documentation, including certificates of analysis and HPLC purity data, is a critical checkpoint before any research use.

What the Citrate Salt Actually Changes

What the Citrate Salt Actually Changes

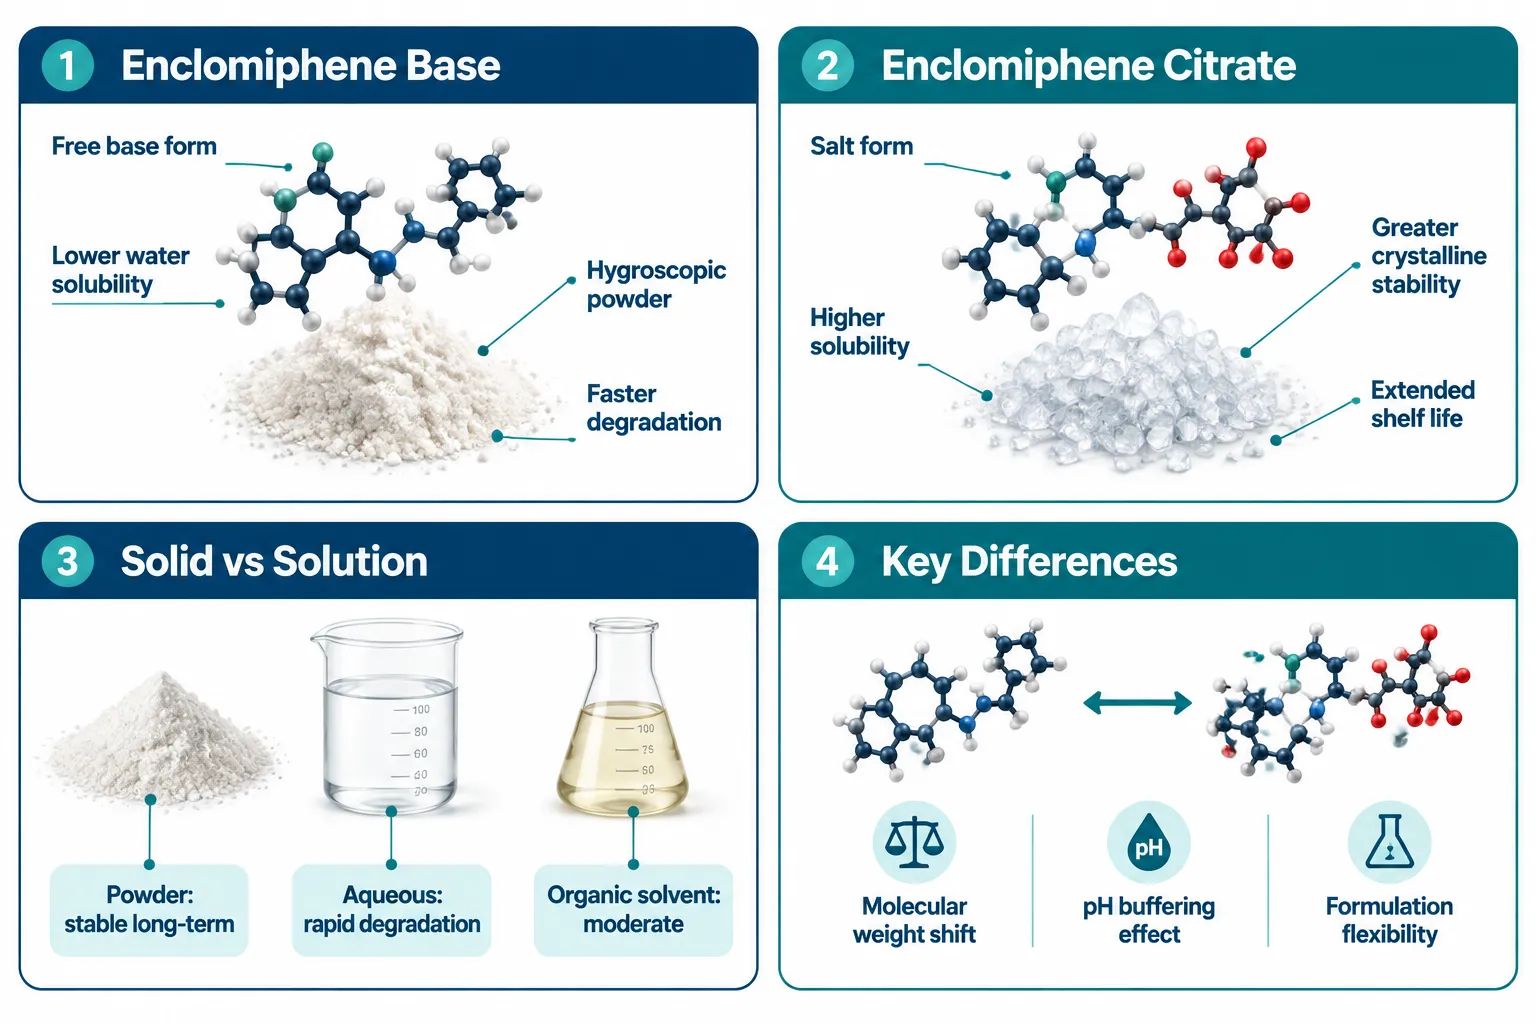
Enclomiphene is the trans-isomer of clomiphene, a selective estrogen receptor modulator with growing research interest in male reproductive endocrinology. When enclomiphene is converted to its citrate salt, a citric acid molecule pairs ionically with the enclomiphene base. This is not a cosmetic change.

The citrate counterion delivers three practical advantages:

Property Enclomiphene (Free Base) Enclomiphene Citrate
Water solubility Low Moderately higher
Crystalline stability Moderate Greater
Formulation flexibility Limited Broader
Hygroscopicity High Reduced

The increased water solubility of the citrate form matters when preparing stock solutions for in vitro work. The free base requires organic solvents such as DMSO or ethanol to dissolve reliably, and those solvents introduce their own biological variables at higher concentrations. The citrate salt can often be dissolved in aqueous buffers at research-relevant concentrations, which simplifies assay design.

"The choice between enclomiphene base and enclomiphene citrate is not arbitrary, it directly affects dissolution behavior, solution stability, and the reproducibility of downstream assays."

The molecular weight difference between the two forms is also worth noting. Enclomiphene free base has a molecular weight of approximately 406 g/mol, while the citrate salt sits closer to 598 g/mol. Researchers calculating molar concentrations must account for this difference to avoid systematic dosing errors across experiments.

This distinction mirrors well-established patterns seen with the parent compound clomiphene citrate, where the salt form has long been preferred for pharmaceutical manufacturing because of its superior stability profile and more predictable dissolution kinetics.

Stability Factors: Light, Moisture, Heat, and Form

Stability Factors: Light, Moisture, Heat, and Form

Both enclomiphene and enclomiphene citrate are susceptible to the same primary degradation drivers: ultraviolet light, ambient moisture, and elevated temperature. However, the degree of vulnerability differs between solid powder, aqueous solution, and organic solution.

Solid Powder Stability

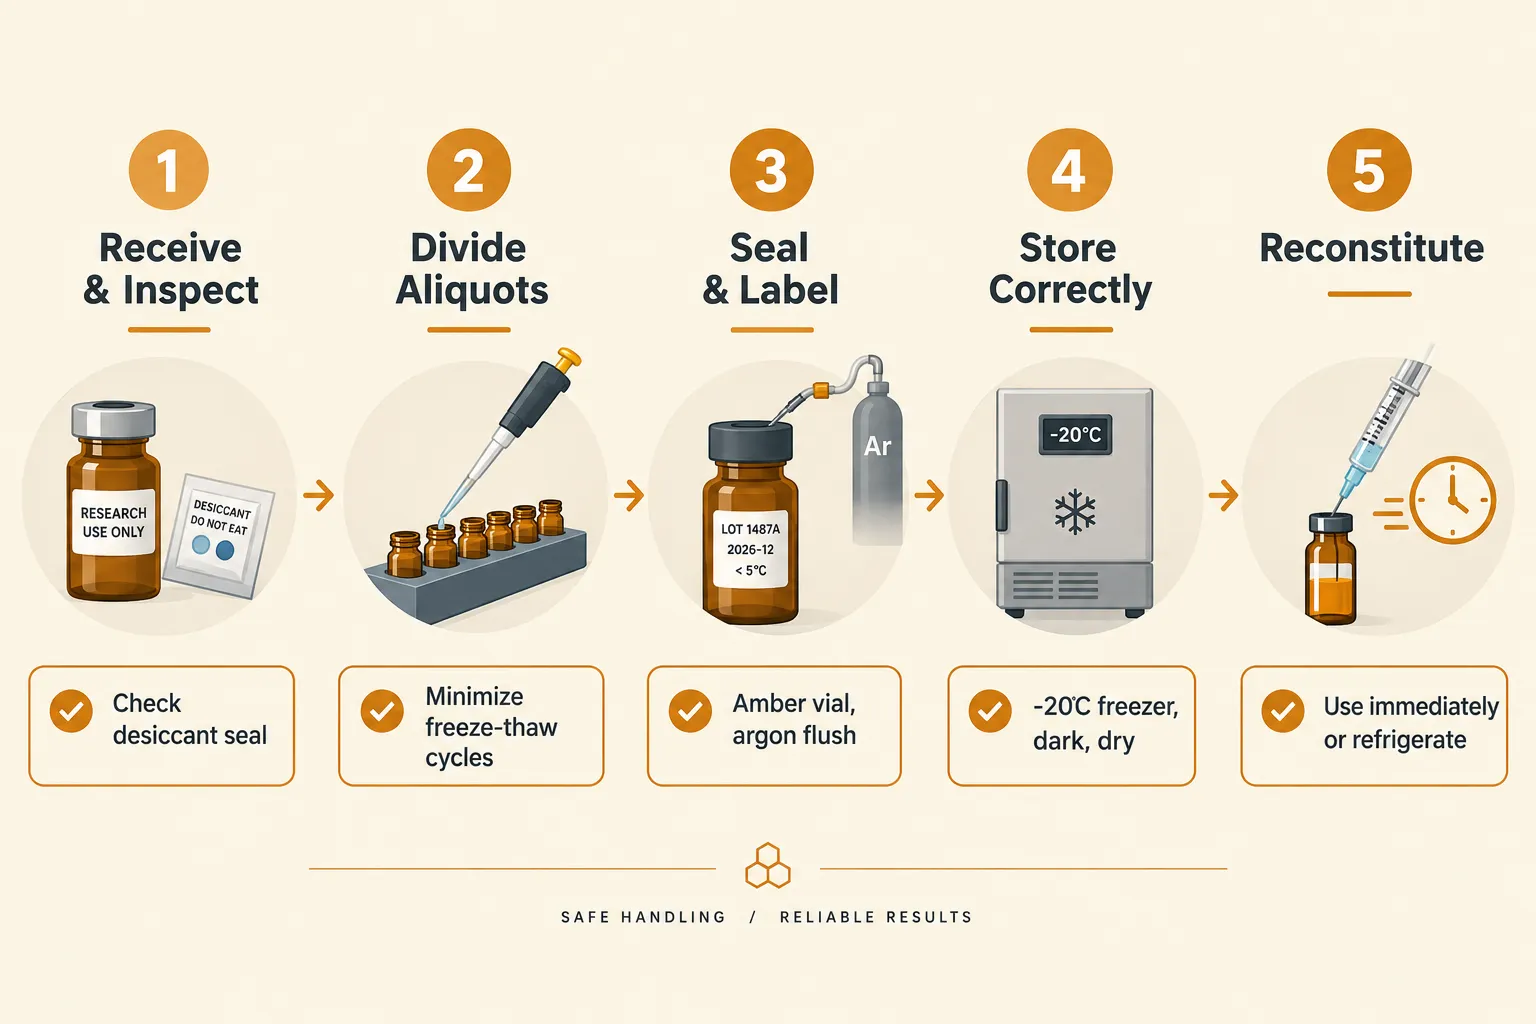
Research-grade powder, whether free base or citrate, is the most stable form. When stored correctly, properly manufactured powder can maintain integrity for 24 months or longer. Correct storage means:

  • Temperature at or below -20 °C for long-term archival
  • Desiccant packs inside a sealed, airtight container
  • Amber or opaque vials to block UV exposure
  • Minimal handling that introduces ambient air or humidity

The citrate form benefits from reduced hygroscopicity relative to the free base. In practical terms, this means the citrate powder is less likely to absorb atmospheric moisture during brief handling windows, which is a meaningful advantage in non-controlled lab environments.

Solution Stability

Aqueous solutions of enclomiphene citrate are markedly less stable than the solid form. At room temperature, degradation can become measurable within days. Refrigerated aqueous solutions (2-8 °C) extend working life but should still be used within a short window, typically 48 to 72 hours for research applications.

Organic solvent solutions (DMSO, ethanol) offer moderate stability but are not suitable for extended storage. Freeze-thaw cycling accelerates degradation in both aqueous and organic solutions, which is why aliquoting into single-use volumes before freezing is standard practice.

Finished Formulations

Capsule and liquid suspension formulations of enclomiphene citrate demonstrate extended stability at or below 25 °C when packaged with appropriate moisture barriers. Regulatory stability expectations for finished dosage forms generally require data supporting a shelf life of 24 months under controlled conditions, and enclomiphene citrate formulations have been evaluated under those frameworks in clinical development programs.

Practical Research Handling for Enclomiphene Citrate vs Enclomiphene

Practical Research Handling for Enclomiphene Citrate vs Enclomiphene

Applying the stability science above to day-to-day laboratory practice requires a clear protocol. The following guidance applies to both forms but is especially relevant for enclomiphene citrate given its broader use in research pipelines.

Before Use

  • Verify the certificate of analysis (COA) from the supplier, confirming HPLC purity of 98% or above
  • Confirm the compound is labeled correctly as citrate salt or free base, the two are not interchangeable in concentration calculations
  • Inspect the desiccant seal; a broken seal is grounds for rejection

During Reconstitution

  • Warm sealed vials to room temperature before opening to prevent condensation on the powder
  • Use the appropriate solvent for the form: aqueous buffer for citrate, DMSO or ethanol for free base
  • Prepare only the volume needed; do not reconstitute bulk quantities

During Storage

  • Store reconstituted solutions at 2-8 °C and use within 48-72 hours
  • Store dry powder at -20 °C in amber vials with desiccant
  • Log every freeze-thaw cycle; limit to no more than two per aliquot

Researchers sourcing serms for comparative studies should apply the same handling discipline to related compounds. For those working with peptide-based research compounds alongside small-molecule serms, foundational guidance on compound classes is available in resources covering peptides 101 for research-use only buyers.

Vendor selection is equally important. A vendor scoring rubric that evaluates third-party testing, cold-chain shipping, and documentation practices will reduce the risk of receiving degraded or mislabeled material. Researchers running multi-compound protocols, for example, pairing a serm with a growth hormone secretagogue, can find relevant product context in resources such as the IPA Sermorelin stack research overview.

For those evaluating research-grade serm products specifically, the serm 10mg product page provides purity and specification details relevant to procurement decisions.

Conclusion

The distinction between enclomiphene citrate and enclomiphene free base is not semantic. The citrate salt offers measurably better crystalline stability, reduced hygroscopicity, and broader formulation options, but it also carries a different molecular weight that must be factored into every concentration calculation. Both forms demand cold, dark, dry storage in the solid state, and both degrade significantly faster once dissolved.

Actionable next steps for researchers in 2026:

  1. Audit current stock: confirm whether materials on hand are labeled as citrate salt or free base and recalculate molar concentrations accordingly.
  2. Implement single-use aliquoting before freezing to eliminate freeze-thaw degradation.
  3. Require HPLC-verified COAs from all suppliers before accepting shipments.
  4. Establish a 48-72 hour use window for all reconstituted solutions stored at 2-8 °C.
  5. Apply the same vendor documentation standards to all research compounds, not just serms.

Reproducibility in enclomiphene research depends on treating the compound form as a controlled variable, not an afterthought.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/enclomiphene-citrate-vs-enclomiphene-stability-storage-and-research-handling.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-15 13:04:102026-09-15 13:04:10Enclomiphene Citrate vs Enclomiphene: Stability, Storage, and Research Handling
Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research

Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research

September 12, 2026/0 Comments/in Uncategorized/by

Nearly one in eight men will receive a prostate cancer diagnosis during their lifetime, making prostate-specific antigen one of the most scrutinized biomarkers in all of medicine. As research into hormone-modulating compounds accelerates, particularly selective estrogen receptor modulators like enclomiphene and polypeptide agents such as GLP-1 and GLP-3 analogs, laboratories and clinicians face a practical question: how does PSA monitoring integrate with these newer interventions? Understanding Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research is no longer a niche concern; it sits at the intersection of endocrinology, oncology safety, and advanced peptide science.

Key Takeaways

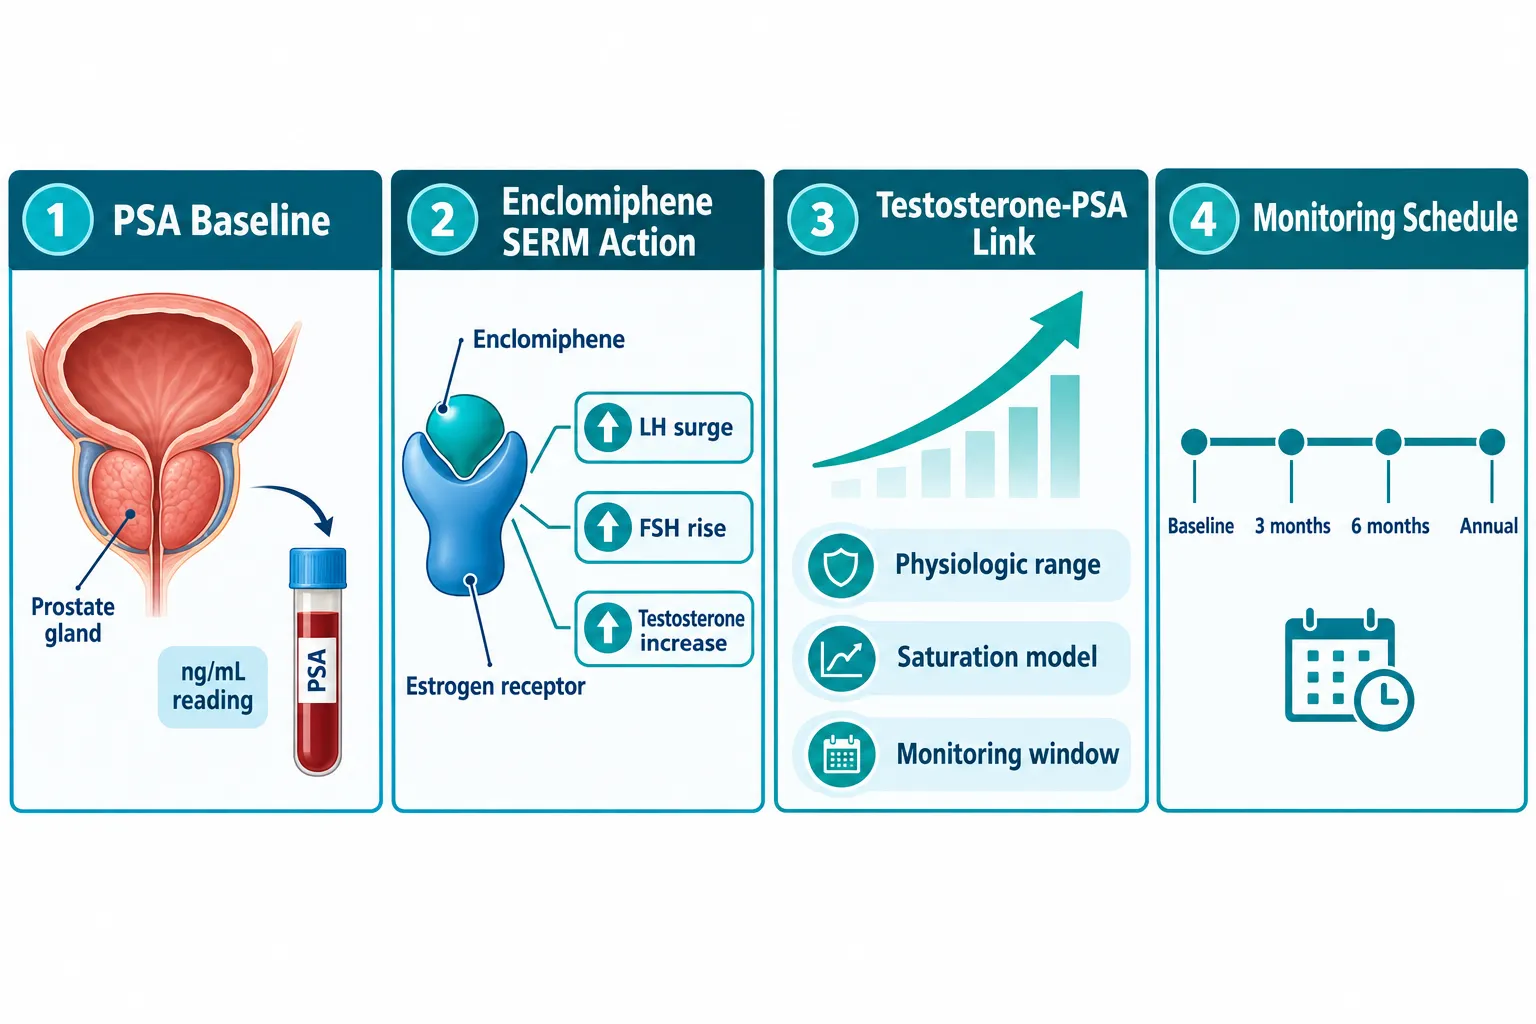
  • PSA is a serine protease produced by prostate epithelium; any intervention that raises testosterone, including enclomiphene, can modestly influence PSA values.
  • Phase III enclomiphene trials have not demonstrated a statistically significant increase in PSA or a clear prostate cancer signal compared with placebo.
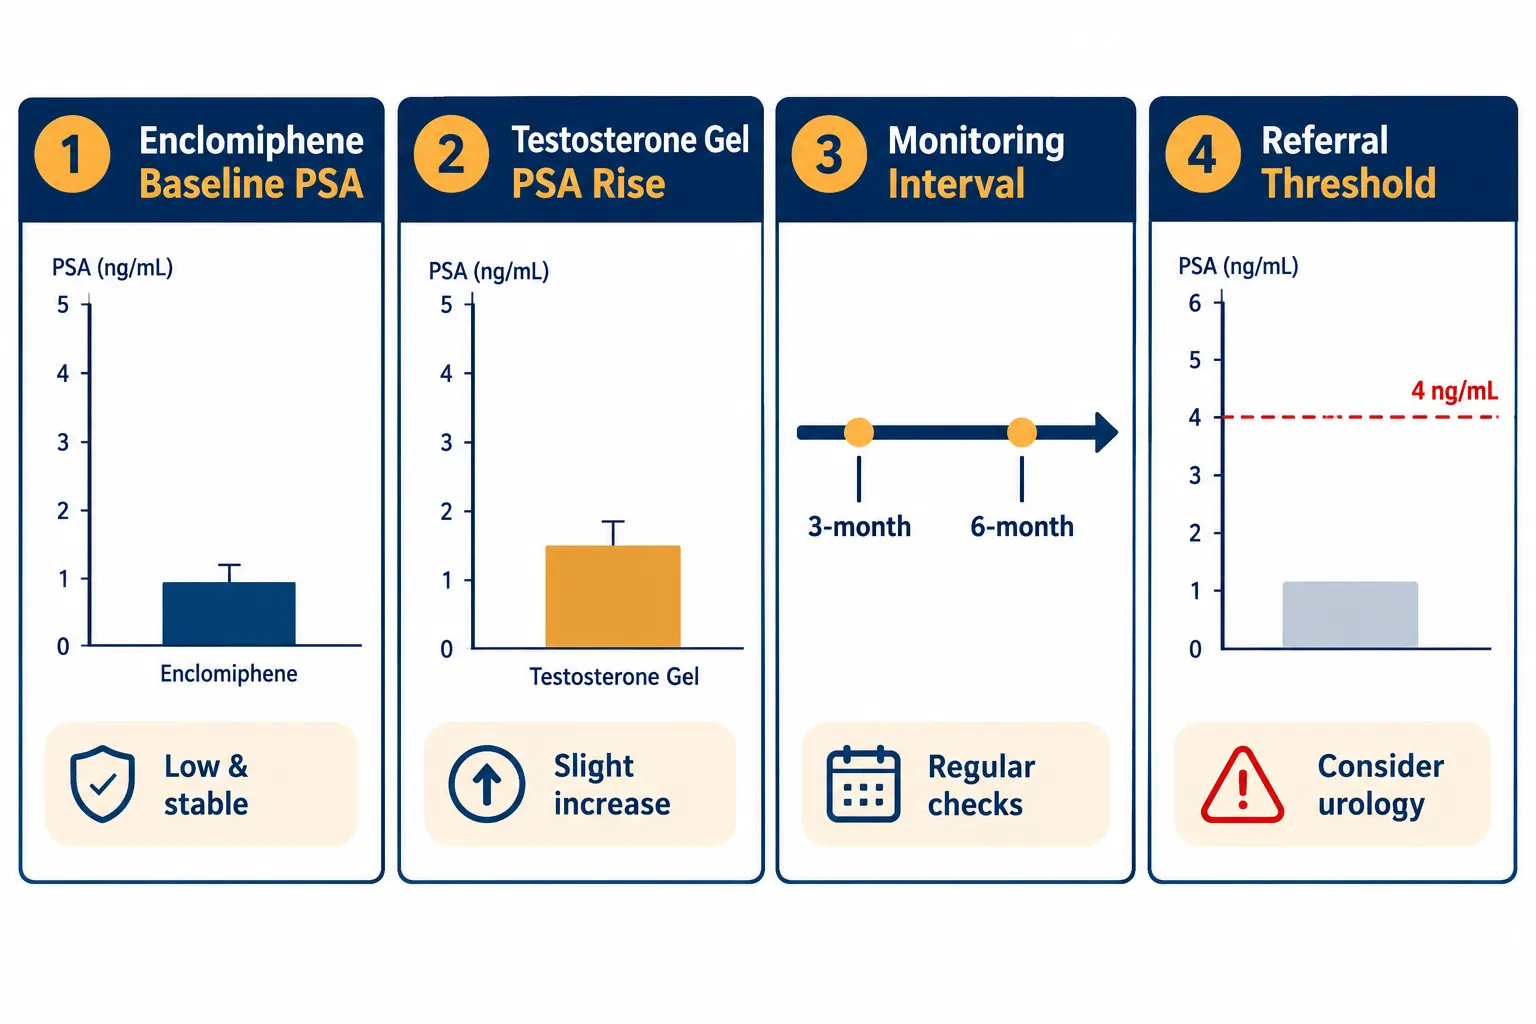
  • Standard monitoring practice mirrors testosterone-replacement protocols: baseline PSA, repeat at 3 and 6 months, then periodic review.
  • GLP-class peptides (GLP-1, GLP-3 analogs such as retatrutide) are not currently integrated into PSA-specific monitoring frameworks; their research focus remains metabolic and cardiovascular.
  • PSA monitoring functions as a safety net, not as evidence that hormone-modulating therapy causes prostate cancer.

What Is PSA and Why Does Hormone Status Matter

What Is PSA and Why Does Hormone Status Matter

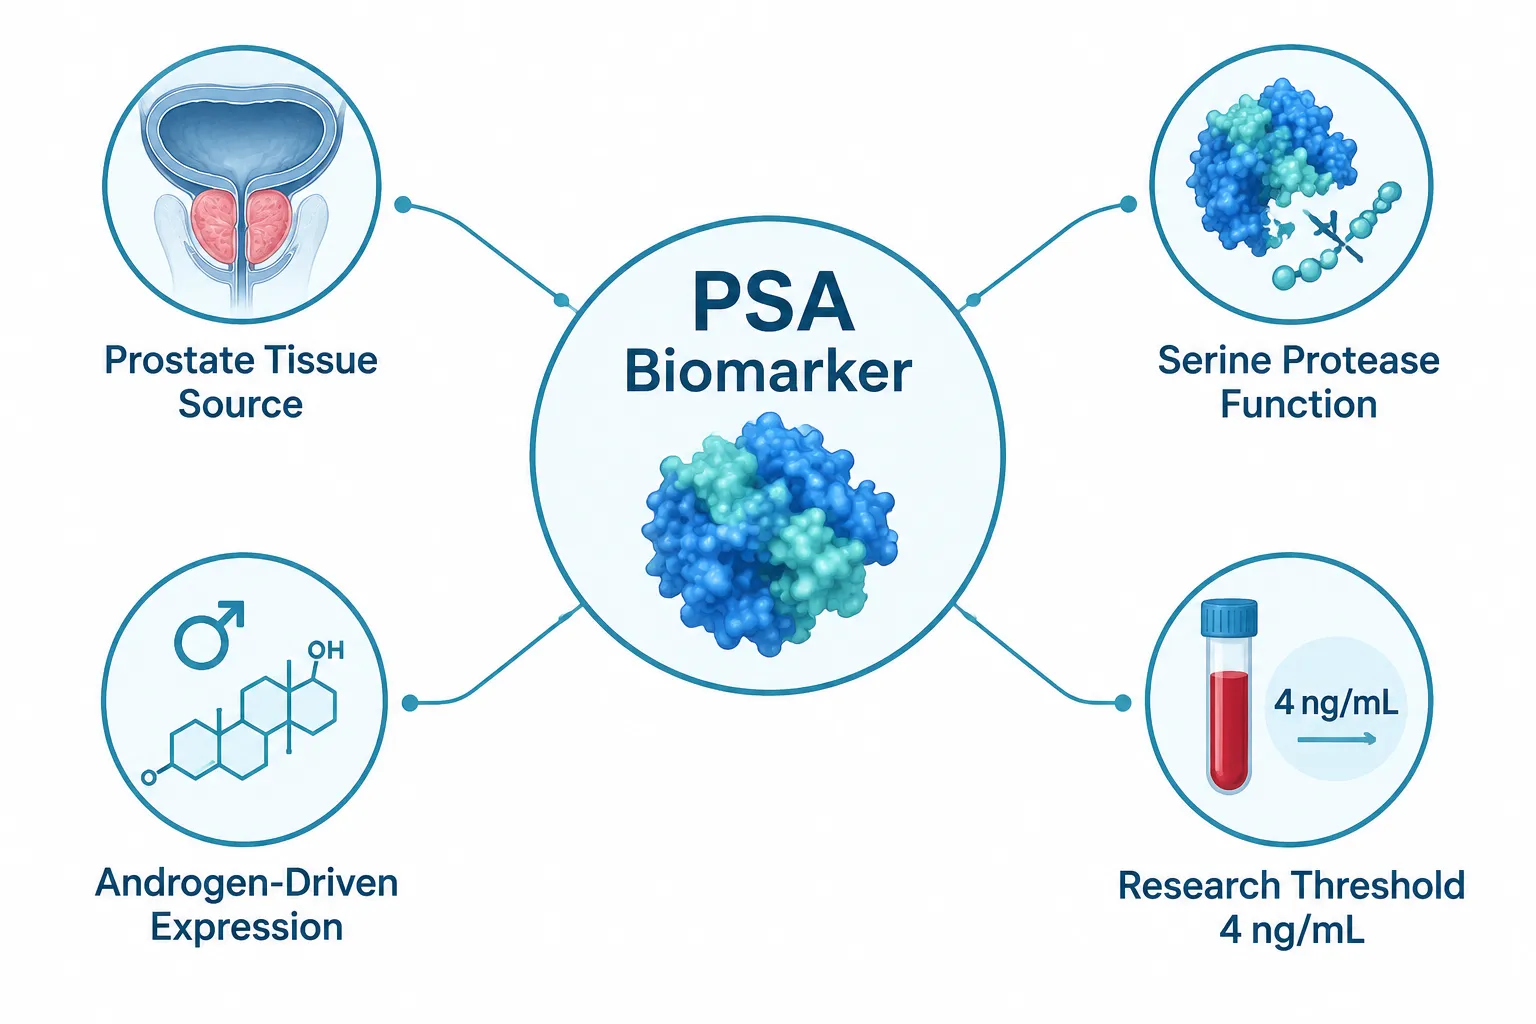
Prostate-specific antigen is a serine protease encoded by the KLK3 gene and secreted almost exclusively by prostate epithelial cells. Its primary physiologic role is liquefying seminal fluid, but because it leaks into circulation in proportion to prostate tissue volume and disruption, serum PSA has become the standard screening tool for prostate pathology.

Why does testosterone matter to PSA? Androgen receptors in prostate tissue directly regulate KLK3 transcription. When testosterone rises, whether from exogenous replacement or from endogenous stimulation, prostate cells can increase PSA secretion. This relationship is real but not linear. The "saturation model" of prostate androgen biology proposes that androgen receptors become fully occupied at relatively low testosterone concentrations (roughly 200-250 ng/dL), meaning that moving from low-normal to high-normal testosterone produces far less incremental PSA change than moving from castrate levels to low-normal. This model has important implications for how researchers interpret PSA data in enclomiphene studies.

Researchers exploring enclomiphene in male endocrine research and LH, FSH, and testosterone signaling need to understand this saturation dynamic before drawing conclusions from PSA fluctuations in study subjects.

Enclomiphene and PSA: What the Evidence Shows in 2026

Enclomiphene and PSA: What the Evidence Shows in 2026

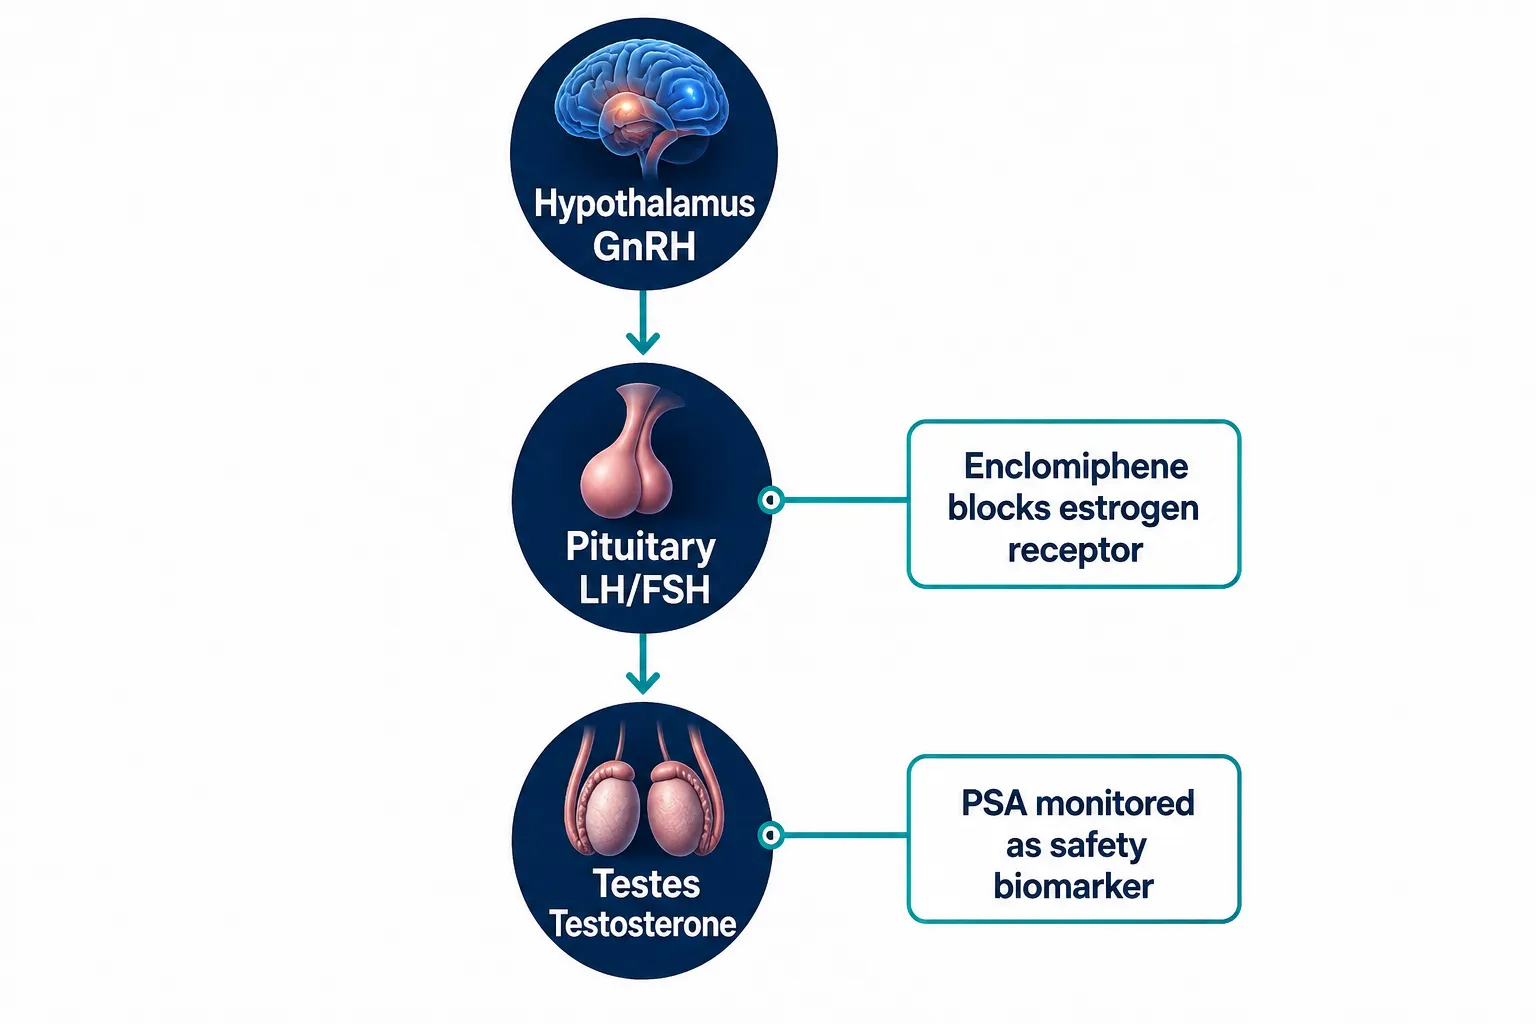
Enclomiphene is the trans-isomer of clomiphene citrate. Unlike the mixed-isomer parent compound, it acts as a pure estrogen receptor antagonist at the hypothalamic-pituitary axis, blocking negative feedback and driving endogenous LH and FSH secretion, which in turn stimulates testicular testosterone production. This mechanism makes it conceptually distinct from exogenous testosterone, yet the downstream effect on prostate tissue is similar: higher circulating testosterone.

Phase III trials enrolling up to approximately 354 men over roughly six months have not shown a statistically significant PSA increase compared with placebo. No trial to date has demonstrated a cancer-incidence signal attributable to enclomiphene. Older comparative data pitting oral enclomiphene against transdermal testosterone gels found only small, clinically insignificant PSA changes with enclomiphene, changes that were not consistently observed with gels, suggesting that endogenous stimulation via a serm may affect PSA differently than direct exogenous androgen delivery.

For researchers building study designs, understanding how serms interact with polypeptide hormones in research provides essential context for interpreting hormone panels alongside PSA data.

Practical PSA Monitoring Thresholds

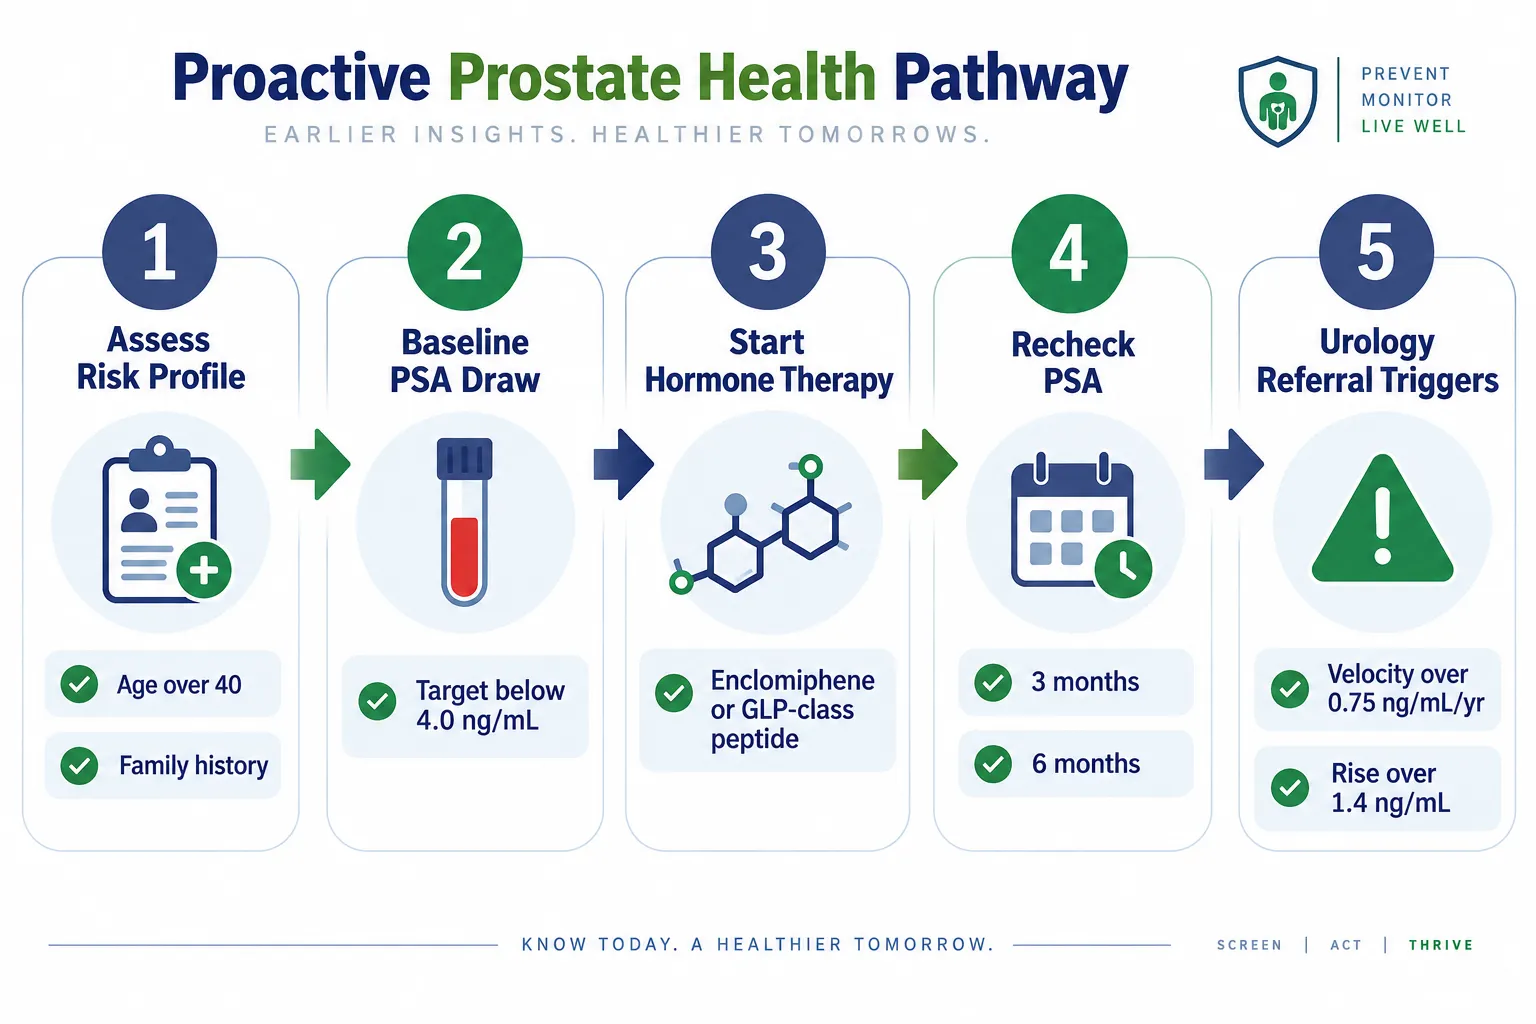
Current clinical guidance, updated through 2026, recommends the following framework for men receiving enclomiphene:

Checkpoint Action
Before starting (all men over 40) Obtain baseline PSA
Baseline PSA > 4.0 ng/mL Urology clearance before proceeding
Baseline PSA > 3.0 ng/mL + first-degree family history Urology clearance before proceeding
3-month recheck Compare with baseline; note velocity
6-month recheck Continue periodic monitoring
PSA rise > 1.4 ng/mL in any 3-12-month window Urology referral
PSA velocity > 0.75 ng/mL per year Urology referral

This framework mirrors Endocrine Society hypogonadism guidelines, which state that any testosterone-raising therapy, including enclomiphene, should be avoided in men with known prostate cancer, palpable nodules, or markedly elevated PSA at baseline.

GLP-Class Peptides and the PSA Interface: Where Research Stands

GLP-Class Peptides and the PSA Interface: Where Research Stands

GLP-1 receptor agonists and the newer triple-agonist GLP-3 class agents (such as retatrutide) have generated enormous research interest for their metabolic and cardiovascular effects. Researchers following GLP-3 retatrutide and triple-agonist peptide phase 3 obesity data will note that current endocrine and urology guidance does not integrate GLP-class agents into PSA-specific monitoring frameworks.

This absence is meaningful, not an oversight. GLP-1 and GLP-3 receptors are expressed in pancreatic beta cells, the gut, the brain, and cardiovascular tissue, but not in prostate epithelium at levels that would be expected to alter PSA transcription. These peptides work through cyclic AMP-mediated pathways that are mechanistically separate from the androgen receptor axis driving PSA production.

Where GLP-class research does intersect with prostate health indirectly:

  • Obesity is an established risk factor for aggressive prostate cancer; GLP-class agents that reduce visceral adiposity may theoretically reduce that background risk over time.
  • Weight loss lowers serum estrogen (produced in adipose tissue), which can slightly alter the testosterone-estrogen ratio, a variable that enclomiphene also modulates.
  • Researchers combining enclomiphene with GLP-class peptides in metabolic models, as explored in work on tesofensine, enclomiphene, and peptide-based approaches in metabolic research, should track PSA as part of a comprehensive safety panel even when GLP agents alone would not require it.

The key principle: PSA monitoring requirements are driven by the testosterone-raising component of any research protocol, not by the GLP-class peptide component.

Prostate Safety in Broader Hormone Research Contexts

Long-term observational data and multiple meta-analyses consistently show that testosterone replacement does not meaningfully accumulate in prostate tissue or provoke major biologic change beyond physiologic ranges. The American Urological Association permits carefully monitored testosterone therapy even in select men on active surveillance for low-risk prostate cancer, provided baseline and serial PSA plus imaging are tracked. This permissive but watchful stance extends logically to enclomiphene, which raises testosterone endogenously rather than exogenously.

Researchers working with growth hormone secretagogues alongside these agents can find relevant mechanistic background in the tesa and ipamorelin comparative analysis of growth hormone secretion mechanisms, as GH-axis peptides also affect body composition in ways that could influence the hormonal milieu relevant to PSA.

Conclusion

Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research comes down to one core principle: PSA is a downstream marker of androgen receptor activity in prostate tissue, and any compound that raises testosterone, directly or indirectly, warrants structured PSA surveillance. Enclomiphene raises endogenous testosterone and therefore fits within established monitoring protocols. GLP-class peptides, by contrast, operate through entirely different receptor pathways and carry no current evidence of PSA influence, though they may alter the broader hormonal environment when combined with serms.

Actionable steps for researchers and clinicians in 2026:

  1. Obtain a baseline PSA in all male subjects over 40 before initiating enclomiphene or any testosterone-raising protocol.
  2. Apply established velocity and threshold triggers (greater than 0.75 ng/mL per year; any single rise exceeding 1.4 ng/mL) to prompt urology evaluation.
  3. Do not apply PSA-specific monitoring requirements to GLP-class peptide protocols unless a testosterone-raising agent is co-administered.
  4. Document PSA alongside full hormone panels (LH, FSH, total and free testosterone) to distinguish therapy-driven changes from pathologic trends.
  5. Review the evolving literature on enclomiphene vs enclomiphene citrate formulation differences to ensure study compounds are correctly characterized before interpreting PSA data.

PSA monitoring is not a reason to avoid hormone-modulating research, it is the tool that makes that research safe and scientifically credible.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-and-hormone-modulating-compounds-how-psa-monitoring-in.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-12 13:12:172026-09-12 13:12:17Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research
Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies

Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies

September 8, 2026/0 Comments/in Uncategorized/by

Fewer than one in five researchers working with hormone-modulating peptides routinely track prostate-specific antigen as a safety endpoint, yet the field of prostate specific antigen and peptide hormones is rapidly reshaping how enclomiphene and GLP-class research studies are designed, monitored, and interpreted. Understanding the intersection of PSA biology with emerging serm and incretin-based research is no longer optional for anyone serious about endocrine safety endpoints.

Key Takeaways

  • PSA is a serine protease produced in prostate tissue and regulated by androgen signaling, making it a logical safety marker in any research protocol that modulates testosterone or related hormones.
  • Enclomiphene studies show small, clinically minor PSA increases compared with testosterone-replacement protocols, but baseline and periodic PSA monitoring remains standard practice.
  • GLP-1 receptor agonist research uses PSA primarily for risk stratification rather than as a direct drug-response marker.
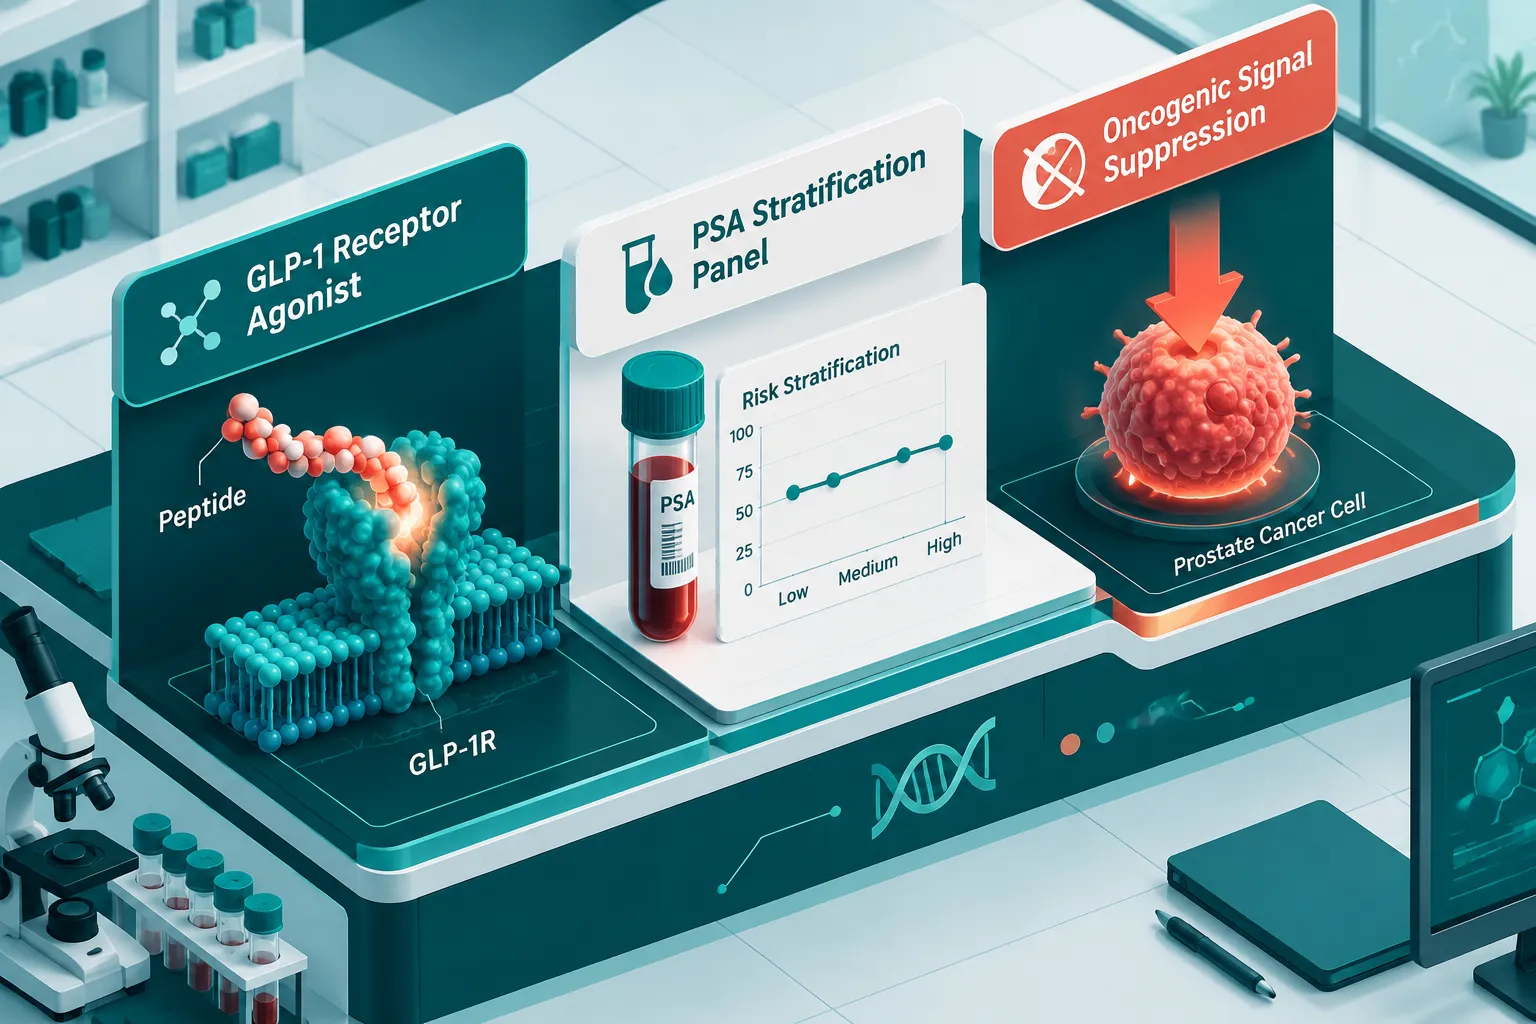
  • Mechanistic data suggest GLP-1 receptor activation may suppress oncogenic signaling in prostate tissue, giving PSA a secondary role as an indirect safety endpoint.
  • Unified PSA monitoring thresholds for enclomiphene and GLP-class research are expected to converge by 2030.

What PSA Is and Why It Matters in Peptide Hormone Research

What PSA Is and Why It Matters in Peptide Hormone Research

Prostate-specific antigen is a serine protease enzyme encoded by the KLK3 gene and secreted almost exclusively by prostate epithelial cells. Its primary physiological role is to liquefy seminal fluid, but because its expression is tightly driven by androgen receptor signaling, serum PSA levels rise and fall in response to changes in the androgen environment.

This androgen-sensitivity is precisely what makes PSA relevant to peptides and polypeptides in endocrine pharmacology. Any compound that raises circulating testosterone, whether a peptide hormone, a serm like enclomiphene, or an exogenous androgen, can theoretically stimulate PSA production. Conversely, compounds that blunt androgen signaling tend to suppress PSA.

Standard PSA thresholds used in research monitoring:

PSA Level (ng/mL) Interpretation in Research Context
Below 1.0 Low baseline; minimal androgen stimulation
1.0-4.0 Normal range; monitor for velocity changes
Above 4.0 Referral threshold; warrants further evaluation
Velocity > 0.75/year Clinically significant rise regardless of absolute value

For researchers working with peptides in basic cell biology and hormone analogues, PSA provides a low-cost, widely available window into androgen-axis activity that complements more expensive genomic or imaging endpoints.

Prostate Specific Antigen and Peptide Hormones in Enclomiphene Monitoring Protocols

Prostate Specific Antigen and Peptide Hormones in Enclomiphene Monitoring Protocols

Enclomiphene citrate is the trans-isomer of clomiphene and acts as a selective estrogen receptor modulator (serm) at the hypothalamic-pituitary axis. By blocking estrogen's negative feedback, it drives a rise in LH and FSH, which in turn stimulates endogenous testosterone production. Because testosterone is the primary driver of PSA expression, any enclomiphene-mediated testosterone increase carries at least a theoretical PSA signal.

Research published through 2025 and reviewed in 2026 consistently shows that enclomiphene produces small but measurable PSA increases, typically within the normal reference range and substantially lower than the rises observed with exogenous testosterone gels or injections. Over follow-up periods extending to three years, no significant PSA impact has been confirmed, though researchers and clinicians continue to advise monitoring because the androgen-axis stimulation is real.

Current enclomiphene PSA monitoring protocol (adapted from testosterone-therapy guidelines):

  1. Establish a baseline PSA before the study compound is introduced.
  2. Repeat PSA at 3 months and 6 months after initiation.
  3. Apply the same 4 ng/mL referral threshold and 0.75 ng/mL/year velocity rule used in testosterone-replacement research.
  4. Document any concurrent medications that could confound PSA (e.g., 5-alpha reductase inhibitors).

The borrowing of thresholds from testosterone-replacement guidelines reflects a practical reality: enclomiphene-specific PSA criteria do not yet exist. Debate continues in the literature about whether early routine PSA checks add meaningful safety data in younger, otherwise healthy research subjects, but baseline and periodic monitoring remain the consensus standard.

"The PSA changes seen with enclomiphene are minor relative to exogenous testosterone, but the absence of dedicated long-term data makes monitoring a non-negotiable safety step in responsible research design."

For a broader view of how enclomiphene fits within receptor biology, the article on enclomiphene and estrogen receptor biology provides useful mechanistic context.

GLP-Class Research Studies and the Role of PSA Risk Stratification

GLP-Class Research Studies and the Role of PSA Risk Stratification

The relationship between prostate specific antigen and peptide hormones in GLP-class research is fundamentally different from the enclomiphene context. GLP-1 receptor agonists, including the triple-agonist retatrutide studied in GLP-3 retatrutide phase 3 trials, do not directly stimulate androgen production. Instead, PSA enters GLP-class research as a risk stratification tool and a secondary safety endpoint.

Large-cohort analyses of GLP-1 receptor agonist users show a neutral to mildly protective prostate-cancer risk profile. Mechanistic studies add an important layer: GLP-1 receptor activation appears to suppress oncogenic signaling pathways in prostate cancer cell lines, suggesting a potential indirect protective effect. PSA is the practical instrument through which researchers detect any meaningful change in prostate cancer risk during these studies.

How PSA functions in GLP-class study designs:

  • Baseline stratification: Subjects with elevated baseline PSA are flagged for exclusion or sub-group analysis to prevent confounding.
  • Case detection: Any PSA rise during a GLP-1 study triggers standard urological workup, separating drug-related from incidental findings.
  • Cardiometabolic integration: PSA is increasingly analyzed alongside insulin resistance markers, visceral fat measurements, and inflammatory biomarkers in risk-reduction models.

This integrated approach is consistent with how carbohydrate antigens and peptide-based assays are being combined with modern research peptide endpoints to build richer safety profiles.

Researchers interested in the metabolic dimensions of GLP-class compounds can also explore tesofensine and metabolic research for a comparative look at how different appetite-modulating agents handle overlapping endpoints.

Where Enclomiphene and GLP-Class PSA Monitoring Are Headed

The convergence of prostate specific antigen and peptide hormones research across serm and incretin platforms is generating pressure for unified monitoring guidelines. Expert commentary in 2026 points toward a likely consensus by 2030 in which:

  • Formal PSA monitoring thresholds specific to enclomiphene will be established, rather than borrowed from testosterone-therapy protocols.
  • PSA dynamics will be incorporated as pre-specified secondary endpoints in GLP-1 and GLP-3 interventional trials, particularly those targeting obesity-related prostate cancer risk.
  • Composite biomarker panels, combining PSA with sex hormone-binding globulin, estradiol, and metabolic markers, will replace single-marker monitoring in advanced study designs.

Understanding how researchers classify hormone analogues and peptide chains is foundational to interpreting these evolving protocols. The overview at peptides in modern research covers the structural and mechanistic distinctions that underpin these monitoring decisions.

Conclusion

The intersection of prostate specific antigen and peptide hormones is no longer a niche concern. For enclomiphene research, PSA monitoring is a borrowed but essential safety practice, one that will likely gain its own dedicated thresholds as long-term data mature. For GLP-class studies, PSA serves a distinct role as a risk stratification and case-detection tool, with emerging mechanistic evidence suggesting these compounds may actually reduce prostate oncogenic signaling.

Actionable next steps for researchers:

  • Establish a documented PSA baseline before initiating any enclomiphene or testosterone-modulating protocol.
  • Apply the 4 ng/mL threshold and 0.75 ng/mL/year velocity rule as interim standards until enclomiphene-specific guidelines are published.
  • In GLP-class study designs, include PSA as a pre-specified secondary safety endpoint with a clear exclusion and referral algorithm.
  • Monitor the literature through 2026-2030 for convergence on unified PSA thresholds across serm and incretin research platforms.
  • Cross-reference PSA data with cardiometabolic and hormonal markers to build more complete safety profiles.

Staying current with these developments positions any research program to meet the higher safety and reporting standards that regulators and peer reviewers will increasingly expect.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-and-peptide-hormones-how-psa-is-used-to-monitor-enclom.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-08 13:08:202026-09-08 13:08:20Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies
Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies

Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies

September 5, 2026/0 Comments/in Uncategorized/by

More than 40 million PSA tests are ordered in the United States each year, making prostate-specific antigen one of the most tracked biomarkers in modern medicine. Yet PSA does not exist in isolation. Increasingly, research programs studying Prostate Specific Antigen, Enclomiphene, and Peptide Hormones are weaving this marker into broader hormone study frameworks, frameworks that now include selective estrogen receptor modulators (serms) like enclomiphene and peptide-based agents in the GLP class. Understanding how labs design these studies reveals why PSA belongs in the same safety panel as testosterone, LH, FSH, and pharmacokinetic peptide data.

Key Takeaways

  • PSA serves as a critical safety biomarker in male hormone studies, including serm trials involving enclomiphene citrate.
  • Enclomiphene raises testosterone while preserving sperm production, distinguishing it from testosterone replacement therapy.
  • GLP-1 receptor agonist trials use ascending-dose, randomized, double-blind designs with composite endpoints.
  • Labs increasingly combine PSA monitoring with peptide pharmacokinetic data to build complete hormonal safety profiles.
  • Regulatory complexity, such as enclomiphene's relationship to clomiphene, directly shapes how study protocols are written.

PSA as a Biomarker in Hormone Research

PSA as a Biomarker in Hormone Research

PSA is a glycoprotein produced by prostate epithelial cells, and its serum level rises when androgen signaling increases. That biological fact makes it indispensable in any study that deliberately elevates testosterone. When a lab designs a serm trial for secondary hypogonadism, the protocol must account for the downstream androgenic effect on prostate tissue, and PSA is the most practical, non-invasive way to do that.

In enclomiphene phase III safety work, clinical laboratory tests form a core safety endpoint alongside physical exams, visual acuity checks, and slit-lamp eye examinations. Although published summaries do not always headline PSA explicitly, practitioners running off-label hormone protocols consistently include it in serial safety panels. The reasoning is straightforward: if enclomiphene successfully raises morning total testosterone from below 300 ng/dL into the normal range, prostate tissue will experience that androgen signal. Monitoring PSA at baseline, mid-study, and endpoint catches any clinically meaningful rise before it becomes a safety event.

Why PSA matters beyond prostate cancer screening:

  • It quantifies androgenic stimulation of prostate tissue in real time.
  • It provides a continuous safety variable rather than a binary pass/fail outcome.
  • It allows dose-adjustment decisions during titration phases.
  • It satisfies FDA expectations for safety data in androgen-modulating drug applications.

For researchers exploring therapeutic peptides alongside serms, PSA anchors the hormone safety panel to a well-validated clinical standard.

How Enclomiphene serm Studies Are Structured

The design of enclomiphene trials illustrates how Prostate Specific Antigen, Enclomiphene, and Peptide Hormones research frameworks are built from the ground up. Enclomiphene citrate is the trans-isomer of clomiphene, and its regulatory path has been complicated precisely because the FDA must decide how to treat the relationship between an isomer and an already-marketed parent compound. As of 2026, an NDA remains in progress with outstanding FDA questions on that relationship.

Phase III enclomiphene trials enrolled men aged 18-65 with secondary hypogonadism, defined as morning total testosterone below 300 ng/dL on two separate occasions with non-elevated LH. The open-label, escalating-dose design started participants at 12.5 mg with titration to 25 mg if needed over six months. The key clinical finding: enclomiphene raises total testosterone into the normal range while preserving LH, FSH, and sperm production, a meaningful advantage over exogenous testosterone replacement, which suppresses the hypothalamic-pituitary-gonadal axis.

"Enclomiphene's ability to maintain spermatogenesis while restoring testosterone makes it a structurally different intervention than TRT, and that difference demands a different safety monitoring strategy."

For more on how serm compounds are categorized and studied, researchers can explore current literature on receptor-selective mechanisms.

Standard safety panel in enclomiphene studies:

Endpoint Category Specific Measures
Androgenic safety PSA, hematocrit, lipid panel
Reproductive hormones Total testosterone, LH, FSH
Ocular safety Visual acuity, slit-lamp exam
General clinical labs CMP, CBC, adverse event log

GLP-Class Peptide Hormone Study Design

GLP-Class Peptide Hormone Study Design

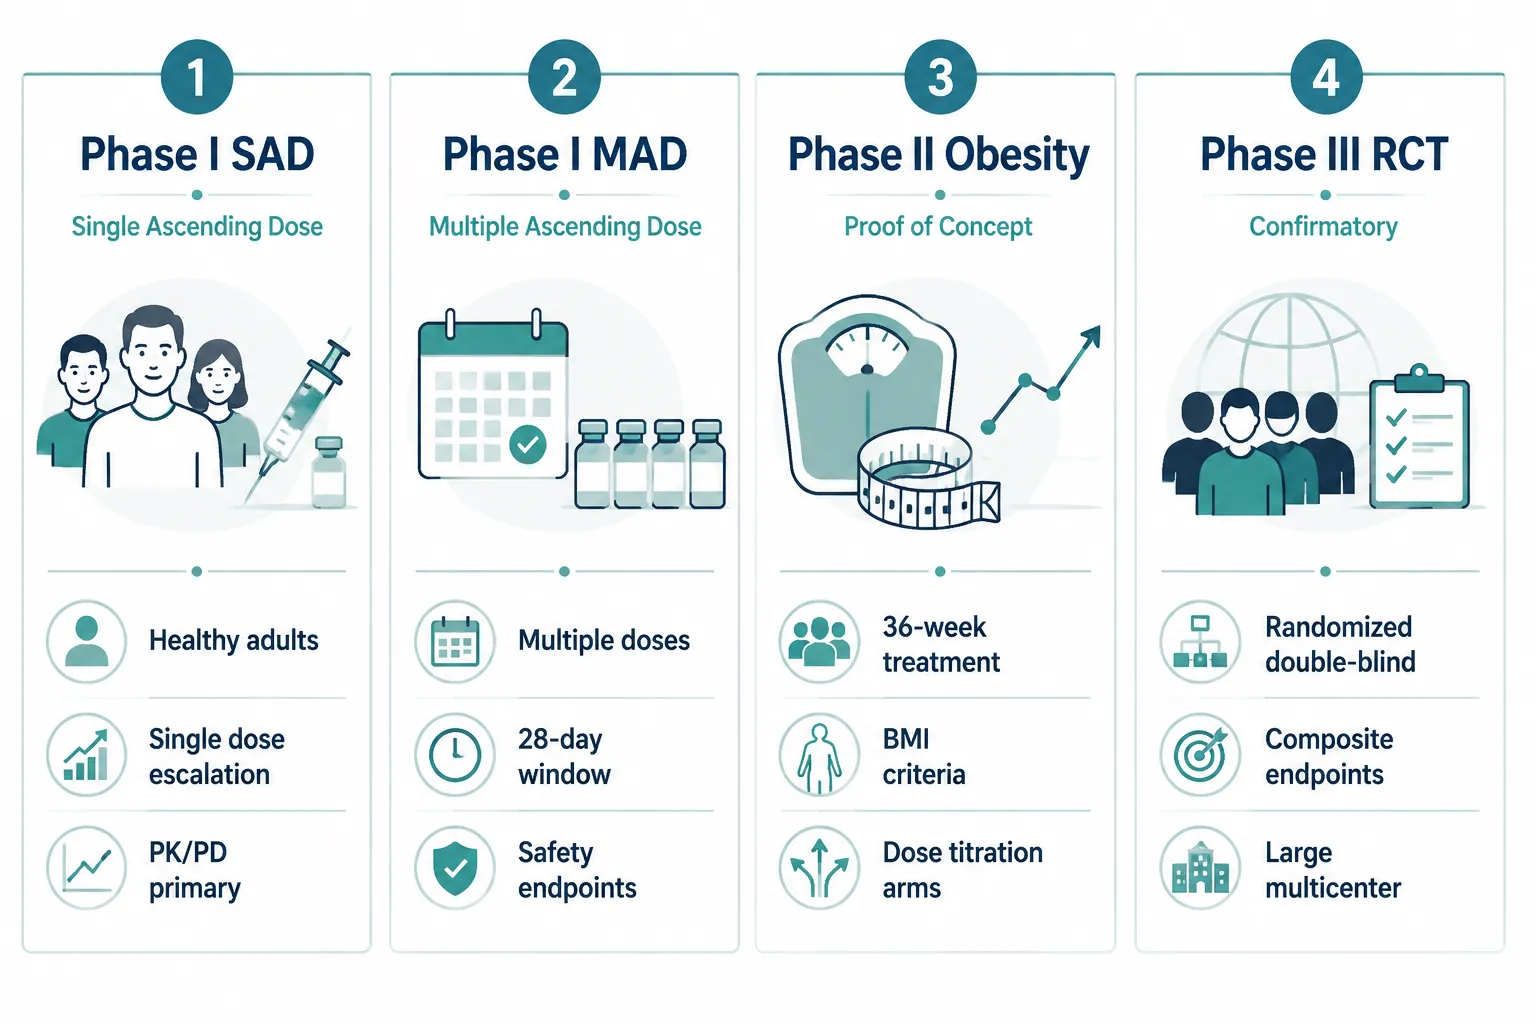
The design logic for GLP-1 receptor agonist studies shares structural DNA with serm trials but diverges sharply in endpoint architecture. A first-in-human phase I study of a novel oral small-molecule GLP-1 receptor agonist illustrates the current template: three sequential parts covering single ascending dose (2.5-50 mg in healthy adults), a 28-day multiple ascending dose in healthy adults, and a 28-day weekly-titration multiple ascending dose in overweight or obese adults. All three parts are randomized, double-blind, and placebo-controlled, with safety and tolerability as primary endpoints and pharmacokinetics and pharmacodynamics as key secondary measures.

When labs repurpose existing GLP-1 agents for new indications, such as substance use disorders or neurodegenerative disease, a common design strategy emerges: keep established metabolic dosing (for example, semaglutide up to 1.0 mg once weekly) and concentrate design innovation on endpoints and patient populations. This approach reduces regulatory uncertainty because pharmacokinetic data already exists.

Researchers interested in signaling peptides and their receptor interactions will recognize that GLP-1 receptor agonists operate through similar second-messenger cascades as other peptide classes, making cross-class study design comparisons genuinely useful.

Key GLP-1 trial design principles in 2026:

  • Integrated cardiometabolic endpoints (cardiovascular events, kidney disease, weight)
  • "Low and slow" titration strategies to balance tolerability with efficacy
  • Real-world data sets used to power sample sizes and set event rate assumptions
  • Bridging studies that connect known pharmacology to new therapeutic uses

For context on how stacking or combining peptide agents affects study design, the discussion of single peptide vs stack approaches is directly relevant to multi-arm GLP-1 trial architectures.

Integrating PSA, serm, and Peptide Data Into a Unified Safety Framework

Integrating PSA, serm, and Peptide Data Into a Unified Safety Framework

The convergence of Prostate Specific Antigen, Enclomiphene, and Peptide Hormones research into unified safety frameworks reflects a broader shift in how hormone studies are powered and monitored. Labs running combination protocols, for instance, pairing a serm with a growth hormone-releasing peptide, must build safety panels that capture both androgenic effects (PSA, hematocrit) and peptide-specific effects (IGF-1, fasting glucose, injection-site reactions).

Research on Sermorelin, Ipamorelin, and CJC-1295 dosage demonstrates how multi-peptide protocols require layered monitoring, just as multi-arm GLP-1 trials require composite endpoint tracking. Similarly, Tesamorelin vs Sermorelin comparisons highlight how small structural differences between peptide agents can produce meaningfully different safety profiles, a lesson directly applicable to enclomiphene's isomeric relationship to clomiphene.

Labs designing these studies in 2026 are also increasingly using next-generation cardio-kidney-metabolic outcome frameworks, which propose explicit design principles emphasizing integrated endpoints, careful patient selection, and robust trial architectures. When PSA is included as a continuous safety variable rather than a binary screening test, it fits naturally within these multi-domain outcome structures.

Practical checklist for integrated hormone study design:

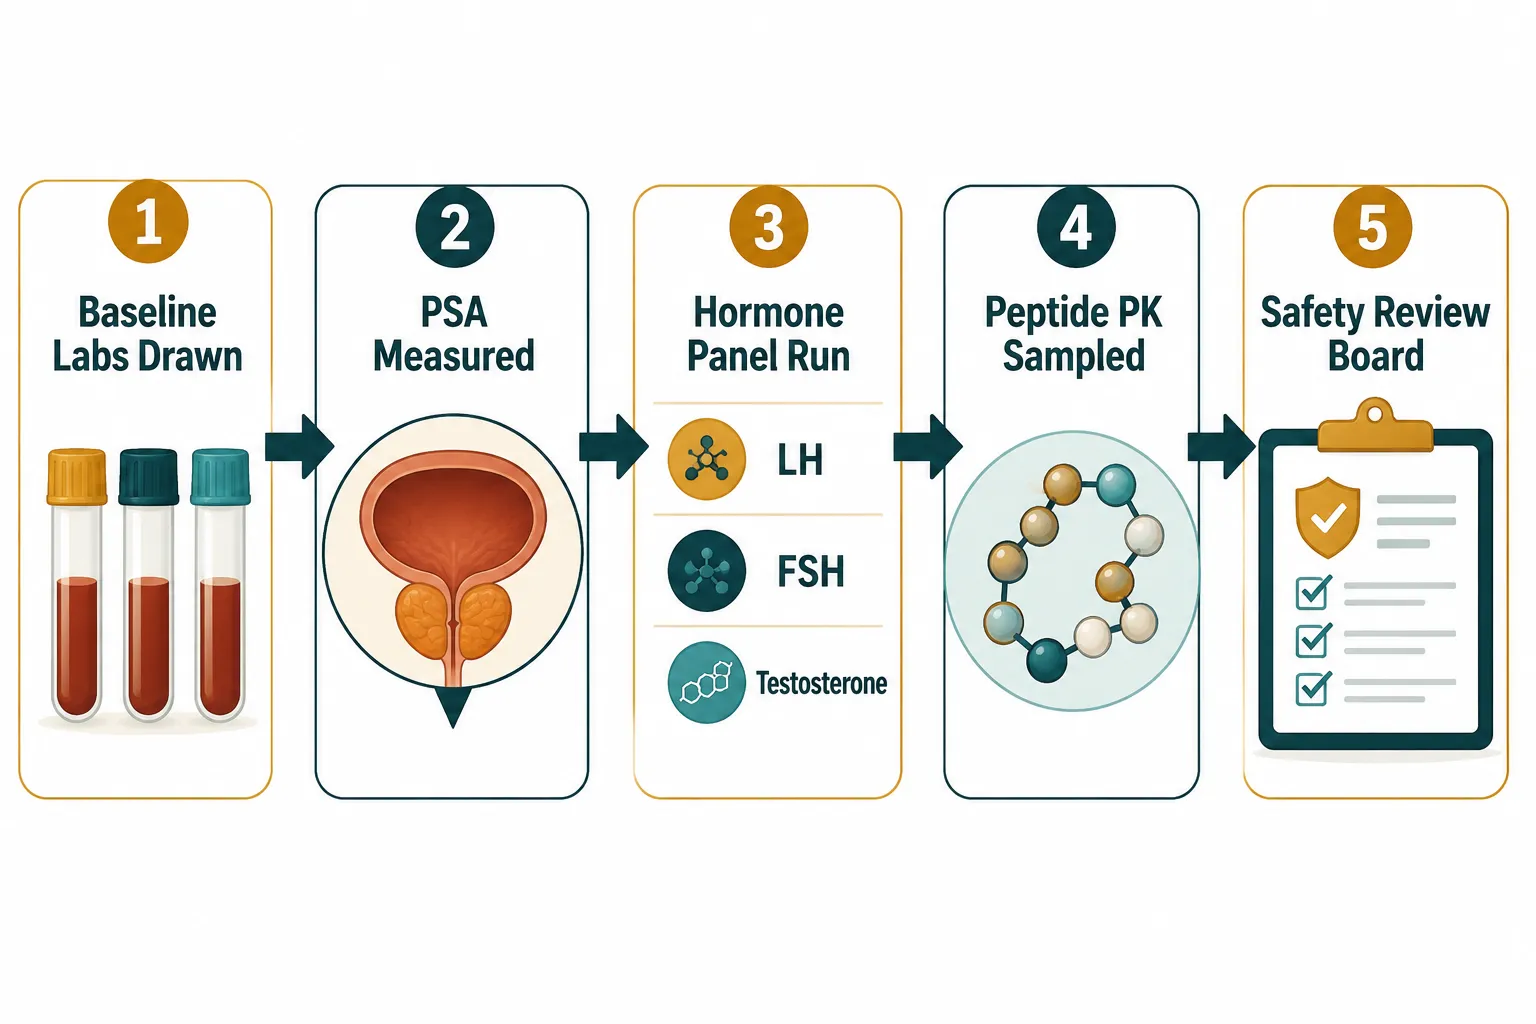
  • Define androgen exposure with testosterone, LH, FSH at baseline and each visit
  • Include PSA at minimum at baseline, 3 months, and endpoint
  • Add peptide-specific PK sampling windows aligned with dosing intervals
  • Pre-specify PSA thresholds that trigger dose hold or discontinuation
  • Align FDA engagement strategy (pre-IND, Type C, pre-NDA meetings) with study design milestones

For labs sourcing research-grade compounds, ensuring purity is non-negotiable. Lab tested peptides with verified certificates of analysis are the baseline standard for any protocol that will generate safety data intended for regulatory review.

Conclusion

The intersection of Prostate Specific Antigen, Enclomiphene, and Peptide Hormones in modern hormone study design is not accidental, it reflects the biological reality that androgen modulation, receptor selectivity, and peptide signaling all converge on shared safety endpoints. PSA is not simply a prostate cancer screening tool; it is a dynamic androgenic biomarker that belongs in every male hormone study protocol.

Actionable next steps for researchers and clinicians:

  1. Include PSA as a continuous safety variable in any serm or androgen-modulating protocol, with pre-specified thresholds for dose adjustment.
  2. Apply GLP-1 trial design principles, ascending dose, randomized, double-blind, composite endpoints, to novel peptide programs wherever regulatory precedent is limited.
  3. Use real-world prescribing data and existing pharmacokinetic datasets to power sample sizes and reduce phase II risk.
  4. Engage FDA early through pre-IND meetings when an investigational compound has a structural relationship to an approved drug, as enclomiphene's path illustrates.
  5. Source only verified, lab tested peptides for any study generating data intended for regulatory submission.

Rigorous study design, comprehensive biomarker panels, and early regulatory alignment are the pillars that turn promising hormone research into actionable clinical evidence.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-enclomiphene-and-peptide-hormones-how-labs-design-serm.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-05 13:05:452026-09-05 13:05:45Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies
Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides

Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides

August 28, 2026/0 Comments/in Uncategorized/by

Fewer than 15% of men diagnosed with functional hypogonadism in 2026 are offered non-testosterone pharmacological alternatives, yet enclomiphene citrate, a selective estrogen receptor modulator (serm), has quietly accumulated a substantial research record that intersects with some of the most active areas in peptide science. Understanding estrogen receptors and enclomiphene, and how serm research interfaces with polypeptide hormones and GLP-class peptides, is no longer a niche academic exercise. It is a practical framework for clinicians, researchers, and informed patients navigating a rapidly expanding hormonal-optimization landscape.

Key Takeaways

  • Enclomiphene blocks hypothalamic estrogen receptors to amplify GnRH, LH, and FSH output, preserving endogenous testosterone production.
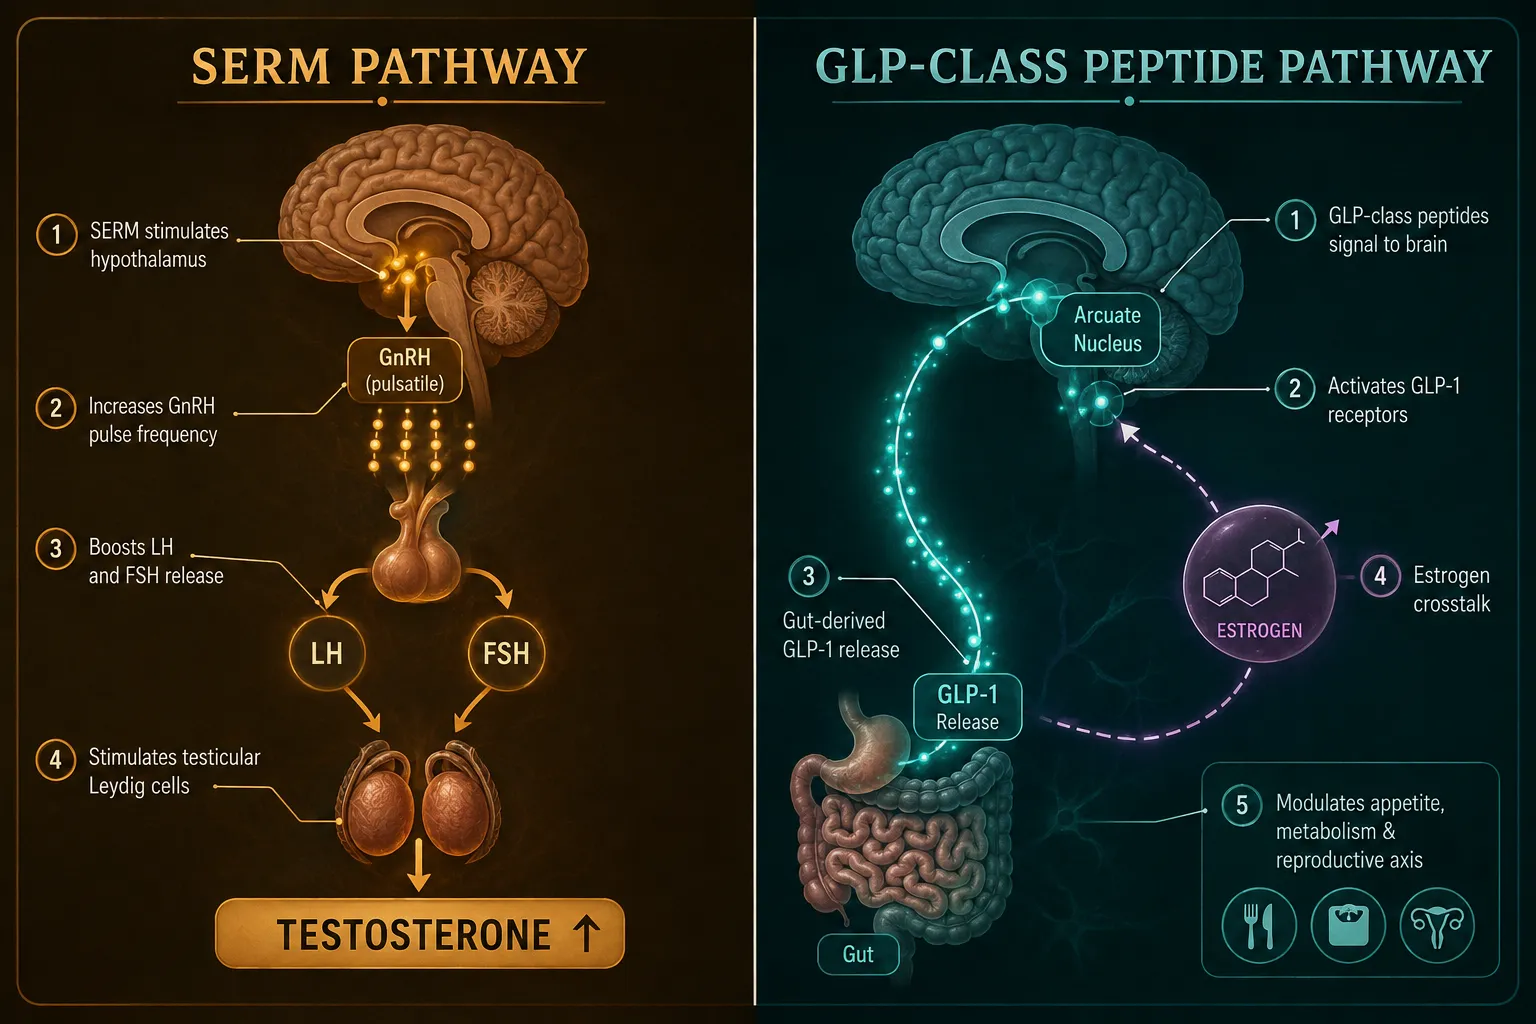
  • Emerging evidence points to a bidirectional crosstalk between estrogen receptor signaling and GLP-1 class peptide pathways, particularly in the arcuate nucleus.
  • Polypeptide hormones such as GHRH analogues and GLP-class peptides operate through distinct receptor families but share downstream metabolic overlap with serm-driven hormonal cascades.
  • As of 2026, enclomiphene remains off-label for male hypogonadism in most jurisdictions, while GLP-1 receptor agonists hold broad regulatory approval.
  • Purity and third-party verification of research peptides are critical variables when studying these interactions at the lab level.

How Enclomiphene Targets Estrogen Receptors

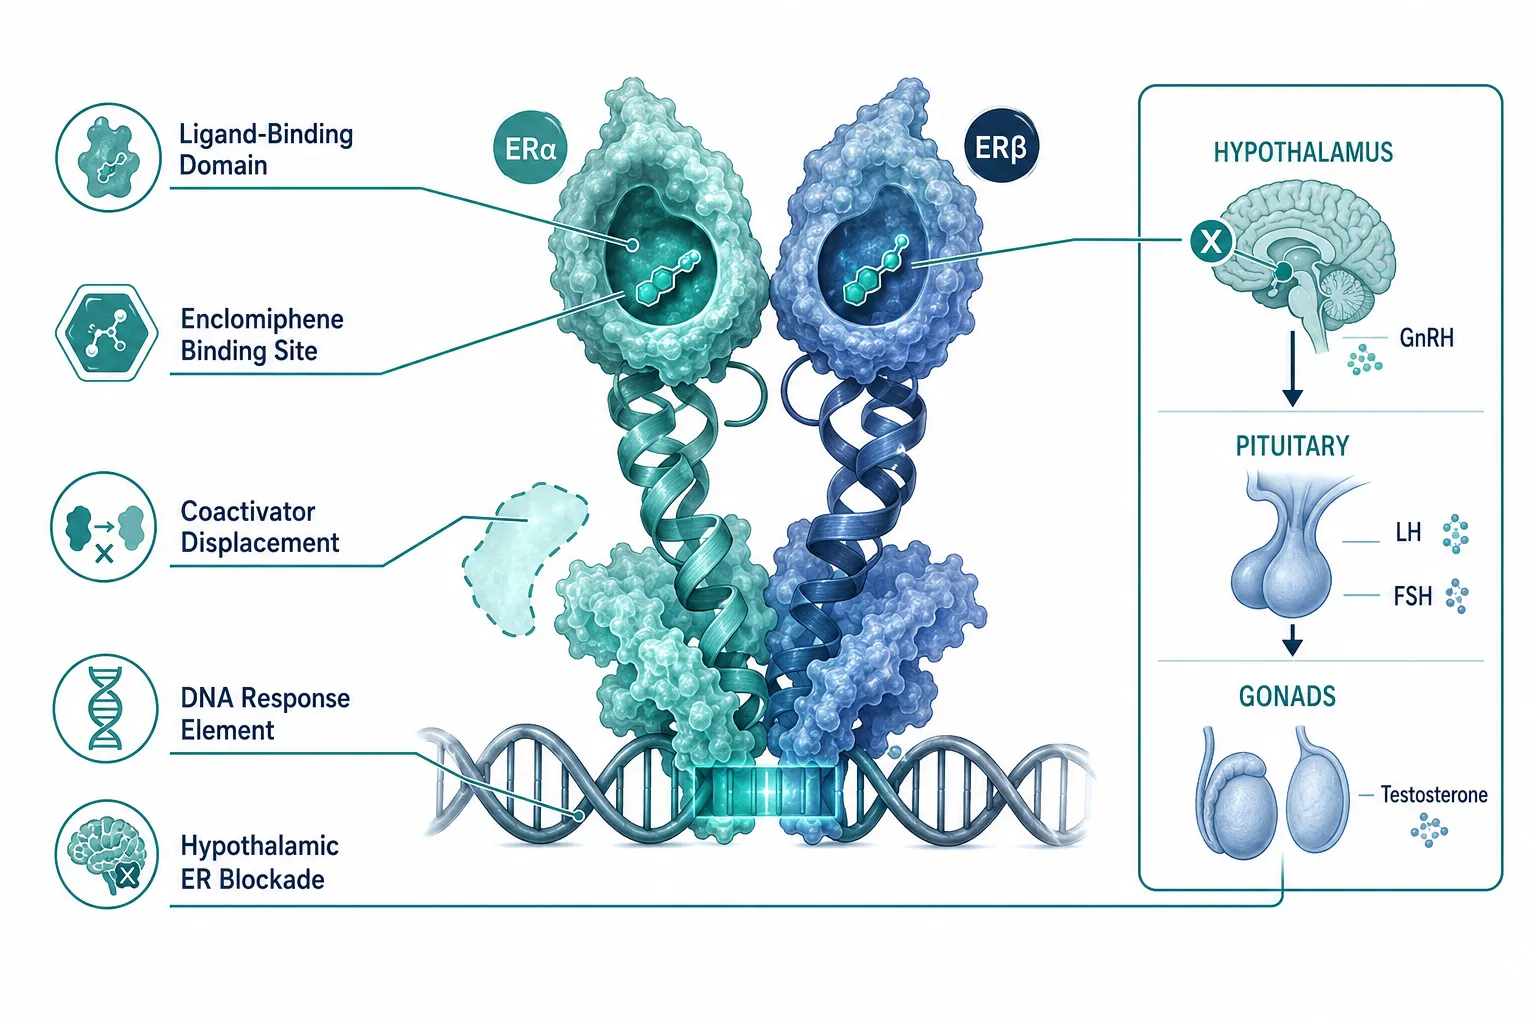
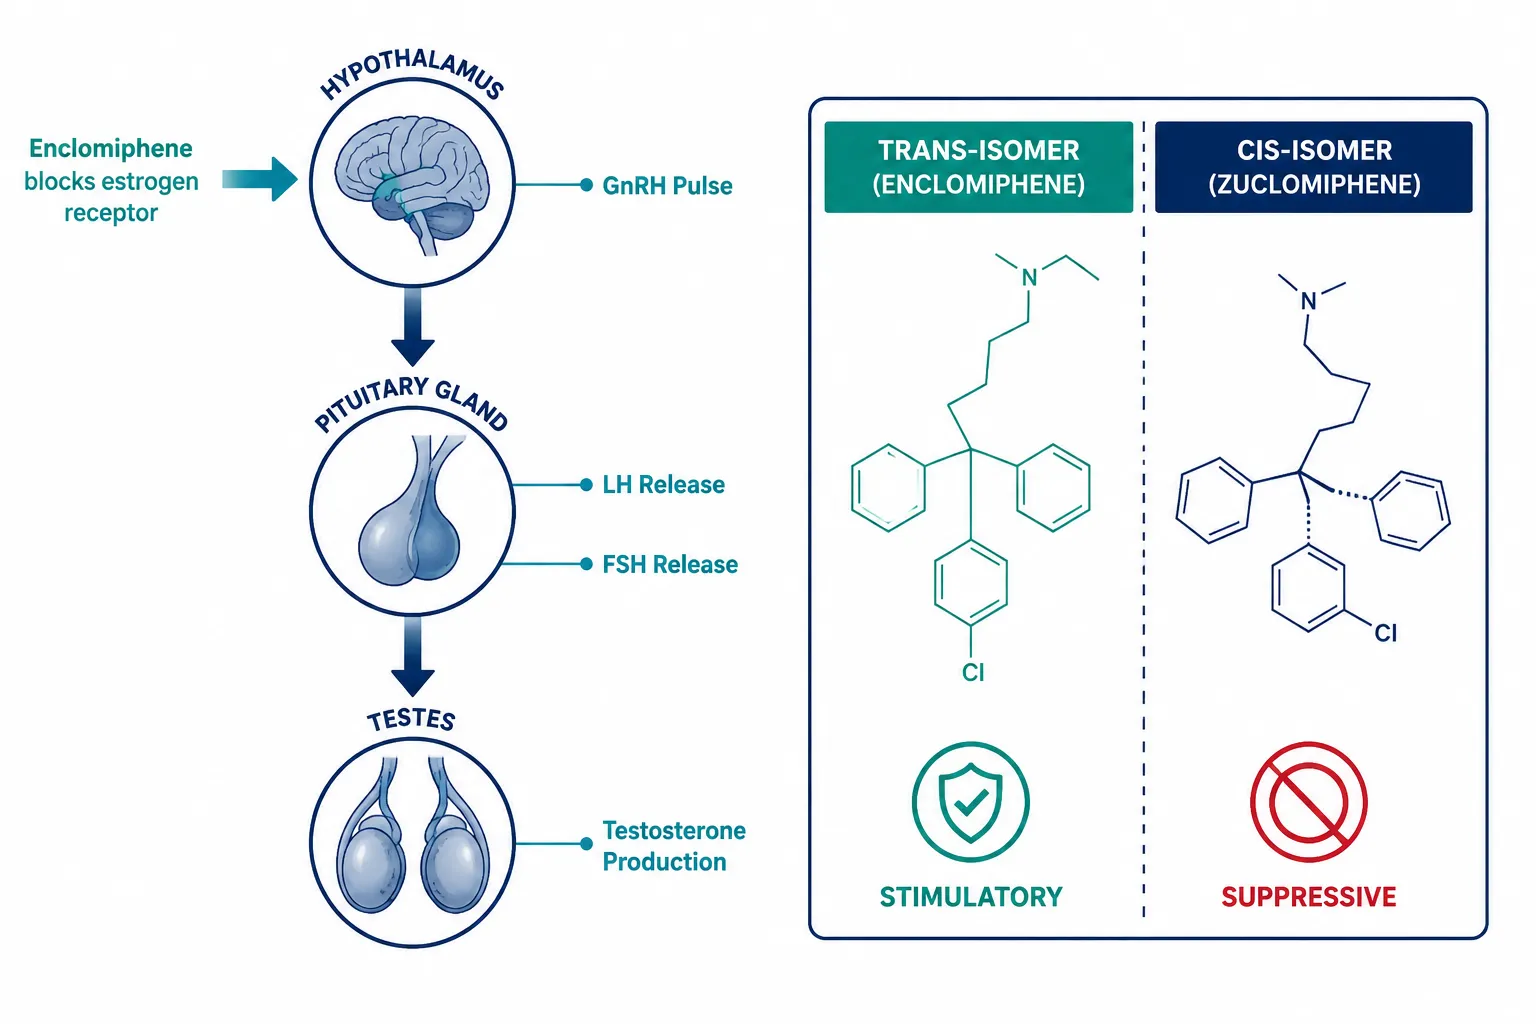
Enclomiphene is the trans-isomer of clomiphene citrate. While clomiphene contains both the zuclomiphene (cis) and enclomiphene (trans) isomers, the trans form carries most of the receptor-antagonist activity at the hypothalamic level. It binds competitively to estrogen receptor alpha (ERa) and estrogen receptor beta (ERb) in the hypothalamus and pituitary, blocking the negative feedback that estradiol normally exerts on gonadotropin-releasing hormone (GnRH) pulsatility.

How Enclomiphene Targets Estrogen Receptors

The result is a measurable increase in GnRH pulse frequency, which drives luteinizing hormone (LH) and follicle-stimulating hormone (FSH) secretion from the anterior pituitary. Elevated LH then stimulates Leydig cell testosterone synthesis in the testes. This mechanism is fundamentally different from exogenous testosterone replacement, which suppresses the hypothalamic-pituitary-gonadal (HPG) axis through negative feedback. Enclomiphene preserves, and actively stimulates, endogenous production.

Key receptor pharmacology points:

  • ERa blockade in the hypothalamus is the primary driver of GnRH disinhibition
  • ERb activity in peripheral tissues influences mood, bone density, and cardiovascular tone
  • Enclomiphene's selectivity profile differs from tamoxifen and raloxifene, making direct class comparisons imprecise

A 2025 systematic review comparing enclomiphene to testosterone replacement in male functional hypogonadism found that enclomiphene produced comparable testosterone normalization while maintaining sperm production, a clinically significant advantage for men of reproductive age.

serm Research Interfaces With Polypeptide Hormones: The HPG-Peptide Connection

The phrase "estrogen receptors and enclomiphene: how serm research interfaces with polypeptide hormones and GLP-class peptides" captures a genuinely complex biological intersection. The HPG axis does not operate in isolation. It is modulated by a network of polypeptide signals, including growth hormone-releasing hormone (GHRH), kisspeptin, and GLP-1 receptor agonists.

serm Research Interfaces With Polypeptide Hormones: The HPG-Peptide Connection

GHRH analogues and the serm context

GHRH analogues such as sermorelin and CJC-1295 stimulate growth hormone (GH) release from the anterior pituitary through GHRH receptor activation. Research into sermorelin and ipamorelin CJC-1295 combinations has shown that GH secretion interacts with sex hormone-binding globulin (SHBG) levels, indirectly influencing free testosterone availability. When enclomiphene raises total testosterone, the concurrent use of GHRH analogues may alter SHBG dynamics, creating a meaningful lab-level variable.

For researchers exploring IPA sermorelin stack protocols, understanding how estrogen receptor modulation affects the downstream hormonal environment is essential for interpreting assay results accurately.

GLP-1 class peptides: the emerging crosstalk

GLP-1 receptor agonists, originally developed for glycemic control, have revealed unexpected neuroendocrine activity. GLP-1 receptors are expressed in the arcuate nucleus of the hypothalamus, a region dense with kisspeptin neurons that directly regulate GnRH pulsatility. Estrogen receptors are co-expressed in the same neuronal populations.

"The arcuate nucleus functions as a convergence point where estrogen signaling, GLP-1 receptor activation, and kisspeptin-driven GnRH control interact in ways that current research is only beginning to map."

This means that a serm like enclomiphene, acting on hypothalamic ERa, may have functional crosstalk with GLP-1 receptor signaling in the same anatomical region. Researchers working with GLP-1 peptides in metabolic or neuroendocrine models should account for this overlap when designing experiments that also involve ER-modulating compounds.

The GLP-2 peptide class, while primarily intestinotrophic, also shows central nervous system expression patterns that warrant attention in multi-peptide research designs.

Research Trajectory and Practical Positioning in 2026

As of 2026, the regulatory landscape remains fragmented. Enclomiphene holds no major market authorization specifically for male hypogonadism in the United States or European Union, though off-label prescribing is common in men's health clinics. GLP-1 receptor agonists, by contrast, carry broad approvals for type 2 diabetes and obesity management, with ongoing trials in cardiovascular and neurodegenerative indications.

Research Trajectory and Practical Positioning in 2026

Positioning comparison at a glance:

Factor Enclomiphene (serm) GLP-1 Class Peptides
Primary target Hypothalamic ERa/ERb GLP-1 receptor (gut, brain)
Regulatory status (2026) Off-label (most jurisdictions) Approved (metabolic indications)
HPG axis effect Stimulatory (raises LH, FSH, T) Indirect (arcuate nucleus crosstalk)
Fertility preservation Yes Not established
Research peptide purity needs High High

For lab-level studies examining these interactions, sourcing lab tested peptides with verified purity documentation is non-negotiable. Contaminants or isomeric impurities can confound receptor-binding assays and produce misleading downstream hormone data.

Researchers interested in the growth hormone axis should also review tesa peptide benefits data, as tesa's effects on visceral fat and IGF-1 levels create additional metabolic variables relevant to any multi-compound hormonal study design.

Forward-looking analyst perspective (speculative): The most likely near-term research direction involves combination protocols that pair serm-driven HPG axis stimulation with GLP-1 receptor agonism to address both hypogonadism and metabolic syndrome simultaneously. This is not yet supported by randomized controlled trial data, but mechanistic rationale is strong enough to justify structured pilot studies.

Conclusion

Estrogen receptors and enclomiphene represent a well-characterized pharmacological axis. How serm research interfaces with polypeptide hormones and GLP-class peptides is a newer and more complex question, one that demands rigorous methodology, verified reagents, and a clear understanding of the convergent biology at the hypothalamic level.

Actionable next steps for researchers and clinicians:

  1. Map estrogen receptor expression alongside GLP-1 receptor distribution in any neuroendocrine study design that involves enclomiphene or related serms.
  2. Account for SHBG dynamics when combining GHRH analogues with serm protocols, as free hormone availability will shift.
  3. Use only third-party verified, lab tested peptides to eliminate purity as a confounding variable.
  4. Monitor the regulatory environment closely, enclomiphene's off-label status may shift as trial data accumulates through 2026 and beyond.
  5. Treat GLP-1 and serm crosstalk findings as hypothesis-generating until controlled trial data is available.

The intersection of serm pharmacology and peptide hormone research is not a fringe topic. It is where the next generation of hormonal optimization protocols will be built.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/estrogen-receptors-and-enclomiphene-how-serm-research-interfaces-with-polypeptid.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-28 13:05:392026-08-28 13:05:39Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides
Enclomiphene vs Enclomiphene Citrate: How Labs Choose Between Research Formulations and Vendors

Enclomiphene vs Enclomiphene Citrate: How Labs Choose Between Research Formulations and Vendors

August 26, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay (≤42 chars): 'Enclomiphene vs Enclomiphene Citrate: How', crisp white sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge. Background: bright clinical research laboratory scene in daylight, glass vials of white crystalline powder, molecular structure diagrams on a lightboard, stainless steel lab bench, clean scientific aesthetic. Teal, navy, and white palette. Editorial magazine-cover quality, high contrast, sharp focus on foreground vials.","content":["Four-panel labelled comparison infographic (1536×1024) on a clean white background with teal-and-navy palette: Panel 1 labeled 'Free Base Form' showing a molecular diagram of enclomiphene with callout lines pointing to 'No salt counterion', 'Higher lipophilicity', 'Solvent-sensitive'; Panel 2 labeled 'Citrate Salt Form' showing enclomiphene citrate molecule with callouts 'Citric acid counterion', 'Better aqueous solubility', 'Standard in clinical trials'; Panel 3 labeled 'Dosing Reference' with callout '12.5-25 mg range'; Panel 4 labeled 'COA Check' with callouts 'Purity %', 'Salt form confirmed', 'HPLC trace'. Thin dividing lines between panels, editorial medical-guide polish, labels 1-6 words each inside 5% safe margin.","Annotated step-by-step numbered flow diagram (1536×1024) on a light gray background with deep teal and charcoal palette showing a lab vendor evaluation process: Step 1 'Request COA' with callout arrow pointing to a document icon labeled 'HPLC + NMR required'; Step 2 'Confirm Salt Form' with callout 'Free base vs citrate'; Step 3 'Check Solvent Compatibility' with callout 'DMSO or aqueous buffer'; Step 4 'Verify Stability Data' with callout 'Storage temp, shelf life'; Step 5 'Cross-reference Literature Dose' with callout '12.5-25 mg citrate standard'. Bold numbered circles in teal, clean sans-serif labels, arrows connecting each step, editorial scientific-guide quality, fully inside 5% safe margins.","Split-screen editorial landscape image (1536×1024): left half shows a close-up of a printed Certificate of Analysis document on a stainless steel lab bench under bright studio lighting, with three short annotation callouts, 'Purity above 98%', 'Salt form declared', 'Endotoxin tested', in teal label boxes with thin pointer lines; right half shows a mid-shot of a South Asian female researcher in her 30s in a white lab coat examining a small amber glass vial against a bright window, expression focused and analytical. High-contrast split composition, navy dividing line down the center, warm daylight on the right, cool studio light on the left, magazine editorial quality."]

Professional landscape hero image () with a reading "Enclomiphene vs Enclomiphene Citrate: How". CRITICAL TYPOGRAPHY RULES:

Only one letter separates the two names on most vendor catalogs, yet that difference carries real consequences for solubility, dosing math, and the validity of comparisons to published clinical data. Understanding the distinction between enclomiphene and enclomiphene citrate is not a trivial naming exercise, it is a foundational step in rigorous procurement for any research program working with selective estrogen receptor modulators (serms).

This guide focuses on the practical purchasing and formulation considerations that matter most: salt forms, solvent compatibility, stability, and how to interpret vendor Certificates of Analysis (COAs) when evaluating enclomiphene vs enclomiphene citrate and choosing between research formulations and vendors.

Key Takeaways

  • Enclomiphene is the free base form; enclomiphene citrate is the salt form created by pairing enclomiphene with citric acid, they are not interchangeable by weight.
  • All major clinical trials have used the citrate salt, making it the reference standard for dose comparisons.
  • The free base form offers higher lipophilicity but lower aqueous solubility, which affects solvent choice in research settings.
  • COA review should confirm salt form, purity by HPLC, and endotoxin levels before any procurement decision is made.
  • Vendor transparency, including NMR data and batch-specific stability information, is the clearest signal of supply chain reliability.

Understanding the Chemistry: Free Base vs Salt Form

Understanding the Chemistry: Free Base vs Salt Form

Enclomiphene is the trans-isomer of clomiphene, a serm that acts on hypothalamic estrogen receptors to stimulate endogenous gonadotropin release. When vendors list "enclomiphene" without qualification, they typically mean the free base form, the molecule without an ionic counterpart. "Enclomiphene citrate" refers to the same active molecule paired with citric acid to form a salt.

Why does this matter for labs?

The molecular weight difference is significant. Enclomiphene free base has a molecular weight of approximately 406 g/mol. Enclomiphene citrate adds the citrate counterion, raising the molecular weight to roughly 598 g/mol. That means a 25 mg dose of enclomiphene citrate does not deliver 25 mg of the active trans-isomer, it delivers proportionally less. Labs that fail to account for this difference will prepare solutions at incorrect molar concentrations, potentially compromising experimental reproducibility.

Solubility profiles also diverge:

Property Enclomiphene (Free Base) Enclomiphene Citrate
Aqueous solubility Low Moderate
Lipophilicity Higher Lower
Preferred solvent DMSO, ethanol Aqueous buffers, DMSO
Clinical trial standard No Yes

For researchers already familiar with sourcing frameworks for other research compounds, such as those described in guides on AOD-9604 storage and traceability, the same principle applies here: salt form affects both preparation protocol and shelf stability.

How Clinical Literature Shapes Formulation Choices

The clinical research record is unambiguous. Studies examining enclomiphene in functional hypogonadism have consistently used the citrate salt, with dosing patterns in trials typically ranging from 12.5 mg to 25 mg of enclomiphene citrate. A 2025 systematic review found that enclomiphene and clomiphene produced comparable testosterone restoration while preserving spermatogenesis, a meaningful distinction from exogenous testosterone therapy.

"Because all published efficacy and safety data reference the citrate salt, labs that use the free base form cannot directly map their in-vitro or preclinical findings onto human clinical benchmarks without a molar conversion step."

This is not a minor administrative detail. It is the difference between research that contributes to a translatable evidence base and research that exists in an isolated methodological silo.

As of mid-2026, no FDA-approved enclomiphene product exists. The compound retains investigational status, which means the regulatory environment for compounding and research supply remains fluid. Labs working in the broader hormone research space should monitor compounding pharmacy guidance closely, as regulatory shifts can affect both availability and permissible formulation types.

How Labs Choose Between Research Formulations and Vendors: A Practical Framework

How Labs Choose Between Research Formulations and Vendors: A Practical Framework

When evaluating enclomiphene vs enclomiphene citrate and choosing between research formulations and vendors, experienced procurement teams apply a structured review process. The following framework reflects best practices drawn from the clinical and regulatory context.

Step 1: Confirm the Salt Form on the COA

Every COA should explicitly state whether the material is the free base or citrate salt. If the document lists only "enclomiphene" without specifying the form, request clarification before purchasing. Ambiguity at this stage is a red flag.

Step 2: Review HPLC Purity Data

Purity should be confirmed by high-performance liquid chromatography (HPLC). Acceptable research-grade purity typically sits at 98% or above. Some vendors also provide nuclear magnetic resonance (NMR) spectroscopy data, which confirms molecular identity, not just purity. NMR data is a strong positive signal of vendor credibility.

Step 3: Check Isomeric Composition

Enclomiphene is the trans-isomer of clomiphene. Vendors sourcing from lower-quality synthesis pipelines may supply material with elevated zuclomiphene (the cis-isomer) contamination. The COA should confirm trans-isomer predominance.

Step 4: Evaluate Solvent Compatibility Documentation

Vendors should provide solubility data specific to the form they are selling. For aqueous-based assay systems, the citrate salt is the practical choice. For lipid-based or organic solvent systems, the free base may be appropriate. This mirrors the solvent-compatibility thinking applied in other research compound categories, including those covered in the GHK-Cu copper peptide sourcing guide.

Step 5: Verify Stability and Storage Specifications

Batch-specific stability data, including recommended storage temperature and projected shelf life, should accompany any research-grade order. Enclomiphene citrate is generally stable at -20°C when stored desiccated and away from light. Free base formulations may require tighter controls depending on the solvent system used.

Labs building out broader serm and peptide research programs can apply similar sourcing discipline across compound classes, the documentation-first approach outlined in resources like the BPC-157 core peptides documentation research guide translates directly to this workflow.

Interpreting COAs and Avoiding Common Vendor Pitfalls

Interpreting COAs and Avoiding Common Vendor Pitfalls

The COA is the single most important document in the vendor evaluation process. A well-constructed COA for enclomiphene citrate should include:

  • Identity confirmation: HPLC chromatogram and NMR spectrum
  • Purity result: Percentage purity with method stated
  • Salt form declaration: Explicit statement of free base or citrate
  • Isomeric ratio: Trans-isomer percentage confirmed
  • Endotoxin testing: Particularly relevant for in-vivo research models
  • Batch number and date: Enables traceability and reorder consistency

Vendors who resist providing full COA documentation, or who supply generic certificates not tied to a specific batch, should be deprioritized regardless of price.

For labs that also work with metabolic or mitochondrial research compounds, the same COA standards apply across the board, as illustrated in sourcing discussions for MOTS-C peptide and mitochondrial biogenesis research and SS-31 mitochondrial research themes.

Conclusion

The distinction between enclomiphene and enclomiphene citrate is not semantic, it is structural, chemical, and methodologically significant. Labs that treat the two names as interchangeable risk dosing errors, compromised data comparability, and wasted resources.

Actionable next steps for research teams:

  1. Audit existing inventory to confirm whether current stock is free base or citrate salt, and recalculate molar concentrations accordingly.
  2. Update procurement checklists to require explicit salt form declaration on all COAs.
  3. Prioritize vendors who supply batch-specific HPLC and NMR data, with confirmed trans-isomer purity above 98%.
  4. Align all dosing references to the citrate salt standard used in published clinical literature (12.5-25 mg range) to maintain translational validity.
  5. Monitor the regulatory environment through mid-2026 and beyond, as the compounding and investigational compound landscape for enclomiphene continues to evolve.

Rigorous formulation awareness is not an obstacle to productive research, it is the foundation that makes research results meaningful.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/enclomiphene-vs-enclomiphene-citrate-how-labs-choose-between-research-formulatio.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-26 13:03:582026-08-26 13:03:58Enclomiphene vs Enclomiphene Citrate: How Labs Choose Between Research Formulations and Vendors
Enclomiphene Citrate: Understanding Its Selective Estrogen Receptor Modulation (serm) and Research Uses

Enclomiphene Citrate: Understanding Its Selective Estrogen Receptor Modulation (serm) and Research Uses

August 26, 2026/0 Comments/in Uncategorized/by

Testosterone levels in men have declined measurably across successive generations, a trend that has pushed researchers toward compounds capable of restoring hormonal balance without suppressing the body's own endocrine signaling. Enclomiphene citrate has emerged as one of the most studied candidates in this space, drawing attention for its targeted receptor activity and its structural separation from older, less selective agents. This article examines enclomiphene citrate: understanding its selective estrogen receptor modulation (serm) and research uses in depth, covering mechanism, isomeric distinction, clinical evidence, and current investigational context as of 2026.

Key Takeaways

  • Enclomiphene citrate is the trans-isomer of clomiphene, acting as a selective estrogen receptor modulator (serm) that blocks estrogen receptors in the hypothalamus and pituitary without the prolonged estrogenic activity of its cis counterpart.
  • By blocking negative feedback on the hypothalamic-pituitary-gonadal (HPG) axis, enclomiphene stimulates endogenous LH and FSH release, raising testosterone while preserving fertility.
  • Research distinguishes enclomiphene from clomiphene primarily through its cleaner receptor profile, shorter half-life, and reduced estrogenic side effects.
  • Clinical studies have demonstrated meaningful testosterone restoration in men with secondary hypogonadism, with a favorable safety profile relative to exogenous testosterone therapy.
  • As of 2026, enclomiphene remains investigational in most regulatory contexts, with active research into compounding, reimbursement, and expanded applications.

How Enclomiphene Citrate Works as a Selective Estrogen Receptor Modulator

Enclomiphene citrate belongs to the broader serm class, compounds that bind estrogen receptors and produce tissue-specific agonist or antagonist effects. Understanding where to buy a serm for research purposes begins with understanding what differentiates one serm from another at the receptor level.

How Enclomiphene Citrate Works as a Selective Estrogen Receptor Modulator

Enclomiphene acts primarily as an estrogen receptor antagonist at the hypothalamus and anterior pituitary. Estrogen normally exerts negative feedback on these structures, suppressing the release of gonadotropin-releasing hormone (GnRH), luteinizing hormone (LH), and follicle-stimulating hormone (FSH). When enclomiphene occupies estrogen receptors at these sites, it blocks that feedback loop. The result is increased GnRH pulsatility, elevated LH and FSH secretion, and downstream stimulation of testicular testosterone production.

This mechanism is described as central HPG axis stimulation, the compound works upstream, preserving the testes' own production capacity rather than replacing testosterone exogenously.

"Enclomiphene's antagonism at hypothalamic estrogen receptors effectively resets the HPG axis signal, making it a mechanistically distinct option from testosterone replacement therapy."

Key receptor-level distinctions include:

  • Tissue selectivity: Antagonist at hypothalamus and pituitary; partial agonist activity is minimal compared to zuclomiphene
  • Binding affinity: High affinity for estrogen receptor alpha (ERa), the dominant receptor subtype in the HPG feedback pathway
  • Duration of action: Shorter half-life than zuclomiphene, reducing accumulation and prolonged estrogenic exposure

Enclomiphene vs. Clomiphene: The Isomeric Distinction That Matters in Research

Clomiphene citrate is a racemic mixture of two geometric isomers: enclomiphene (trans) and zuclomiphene (cis). These isomers share the same molecular formula but differ significantly in their pharmacological behavior.

Enclomiphene vs. Clomiphene: The Isomeric Distinction That Matters in Research

Property Zuclomiphene (Cis) Enclomiphene (Trans)
Receptor activity Partial estrogen agonist Estrogen receptor antagonist
Half-life Long (weeks) Short (days)
HPG axis effect Mixed Clean stimulation
Estrogenic side effects Higher risk Lower risk

Researchers investigating serm comparisons and alternatives consistently highlight this distinction. The prolonged estrogenic activity of zuclomiphene can counteract the very HPG stimulation that makes clomiphene useful, creating noise in study outcomes. Isolating the enclomiphene isomer removes this confound.

This isomeric purity is the central reason enclomiphene has attracted independent research interest. Studies using pure enclomiphene report more consistent testosterone elevation with fewer reports of mood disturbance, visual symptoms, and estrogenic effects that have been associated with mixed clomiphene preparations.

Research Applications of Enclomiphene Citrate: Understanding Its serm Mechanism in Clinical Contexts

The primary research application for enclomiphene citrate: understanding its selective estrogen receptor modulation (serm) and research uses translates most directly into the study of secondary (hypogonadotropic) hypogonadism in men. In this condition, low testosterone results not from testicular failure but from insufficient gonadotropin signaling, exactly the pathway enclomiphene addresses.

Research Applications of Enclomiphene Citrate: Understanding Its serm Mechanism in Clinical Contexts

Key research findings and contexts as of 2026 include:

Male Hypogonadism Studies
Phase II and Phase III trials have demonstrated that enclomiphene raises total testosterone into the normal range (300-1000 ng/dL) in men with secondary hypogonadism, while maintaining or improving sperm parameters, a critical advantage over exogenous testosterone, which suppresses spermatogenesis.

Fertility Preservation
Because enclomiphene preserves FSH signaling to the Sertoli cells, it is studied as a fertility-sparing alternative to testosterone replacement. Men seeking to maintain reproductive capacity while addressing low testosterone represent a significant research population. Researchers exploring serm combinations with peptide protocols have noted complementary effects on the endocrine axis.

Metabolic and Body Composition Research
Testosterone restoration through HPG axis stimulation carries secondary metabolic implications. Studies have tracked improvements in insulin sensitivity, lean mass retention, and fat distribution, areas that intersect with sarcopenia research and age-related muscle loss.

Regulatory and Compounding Landscape
The FDA has not granted enclomiphene full approval as of 2026, though it has been the subject of New Drug Application (NDA) submissions. Compounding pharmacies have supplied enclomiphene under specific regulatory frameworks, though evolving Medicaid and compounding policies have introduced sourcing complexity for research teams. Investigators sourcing serm 10mg research preparations should verify current compliance requirements in their jurisdiction.

Safety Profile
Reported adverse effects in clinical studies have been generally mild. The most commonly noted include headache, nausea, and transient visual disturbances, the latter occurring at lower frequency than with racemic clomiphene. Cardiovascular and hepatic markers have remained stable across reviewed trial durations. Researchers combining enclomiphene with other investigational agents, such as those following serm, Ipamorelin, and CJC-1295 protocols, should account for additive endocrine effects when designing study parameters.

Conclusion

Enclomiphene citrate occupies a precise and well-defined position within the serm class. Its mechanism, estrogen receptor antagonism at the hypothalamus and pituitary, produces upstream HPG axis stimulation that restores endogenous testosterone without suppressing fertility or introducing prolonged estrogenic activity. The isomeric separation from zuclomiphene resolves a long-standing confound in clomiphene research and gives investigators a cleaner pharmacological tool.

Actionable next steps for researchers in 2026:

  1. Review current FDA compounding guidance before sourcing enclomiphene for study use.
  2. Design protocols that distinguish secondary from primary hypogonadism to ensure the HPG-stimulation mechanism is relevant to the study population.
  3. Track both testosterone and gonadotropin levels (LH, FSH) as co-primary endpoints to capture the full mechanistic picture.
  4. Consider fertility and spermatogenesis outcomes as secondary endpoints where applicable.
  5. Consult updated clinical trial registries for ongoing Phase III data that may reshape the regulatory outlook before year-end 2026.

The compound's research trajectory suggests continued relevance in endocrine and reproductive medicine. As regulatory clarity improves and compounding frameworks stabilize, enclomiphene citrate is positioned to move from investigational compound to a more formally recognized therapeutic option.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/enclomiphene-citrate-understanding-its-selective-estrogen-receptor-modulation-se.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-26 13:03:262026-08-26 13:03:26Enclomiphene Citrate: Understanding Its Selective Estrogen Receptor Modulation (serm) and Research Uses
Enclomiphene in Male Endocrine Research: LH, FSH, and Testosterone Signaling Without Clomiphene’s Mixed Isomers

Enclomiphene in Male Endocrine Research: LH, FSH, and Testosterone Signaling Without Clomiphene’s Mixed Isomers

August 21, 2026/0 Comments/in Uncategorized/by

Nearly half of all cases of male hypogonadism are classified as secondary, meaning the problem originates not in the testes but in the signaling chain above them. That distinction matters enormously when evaluating research tools, and it is precisely where enclomiphene in male endocrine research has attracted sustained scientific attention. By targeting the hypothalamic-pituitary-gonadal (HPG) axis as a pure trans-isomer selective estrogen receptor modulator (serm), enclomiphene offers a pharmacologically cleaner lens for studying LH, FSH, and testosterone signaling without clomiphene's mixed isomers complicating the data.

Key Takeaways

  • Enclomiphene is the pure trans-isomer of clomiphene, stripped of the cis-isomer (zuclomiphene) that contributes to estrogenic side effects and signal suppression.
  • It stimulates the HPG axis by blocking hypothalamic estrogen receptors, driving measurable increases in LH, FSH, and downstream testosterone.
  • Research data show enclomiphene preserves spermatogenesis, a key advantage over exogenous testosterone replacement therapy (TRT).
  • Hormone levels elevated by enclomiphene have demonstrated persistence after discontinuation in several study populations.
  • As of 2026, enclomiphene has not received formal regulatory approval for hypogonadism, and its use remains within investigational and research contexts.

The Isomer Problem: Why Clomiphene's Mixed Profile Limits Research Clarity

The Isomer Problem: Why Clomiphene's Mixed Profile Limits Research Clarity

Clomiphene citrate has been used off-label in male endocrine contexts for decades. However, it is a racemic mixture, roughly equal parts trans-clomiphene (enclomiphene) and cis-clomiphene (zuclomiphene). These two isomers behave very differently at estrogen receptors.

Zuclomiphene acts as a partial estrogen agonist and has a much longer half-life, accumulating in tissue over time. This leads to elevated estradiol levels, potential mood disturbances, and visual side effects that have been documented in clinical literature. It also appears to partially suppress the very signaling pathway clomiphene is intended to stimulate.

Enclomiphene, by contrast, functions as a clean estrogen receptor antagonist at the hypothalamus. By occupying estrogen receptors there, it prevents the negative feedback signal that would otherwise suppress gonadotropin-releasing hormone (GnRH) pulsatility. The result is a reliable upstream stimulus for LH and FSH release from the pituitary.

This mechanistic clarity is why researchers exploring hormone research compounds have increasingly distinguished enclomiphene from its parent compound. The mixed-isomer problem in clomiphene is not a minor footnote, it is a confounding variable that makes interpreting hormonal outcomes genuinely difficult.

"Separating the trans-isomer from the cis-isomer is not just a chemistry exercise, it is the difference between a targeted signal and a noisy one."

LH, FSH, and Testosterone Responses in Enclomiphene Research

LH, FSH, and Testosterone Responses in Enclomiphene Research

The hormonal data from enclomiphene studies are among the most compelling aspects of its research profile. Across multiple clinical investigations, enclomiphene administration produced robust, dose-dependent increases in:

  • Luteinizing hormone (LH): Elevated within days of administration, reflecting rapid hypothalamic receptor blockade
  • Follicle-stimulating hormone (FSH): Increased concurrently with LH, supporting both Leydig cell stimulation and spermatogenic signaling
  • Total testosterone: Restored toward or into normal physiological ranges in men with secondary hypogonadism

Critically, these hormonal elevations were achieved while keeping estradiol levels lower than those observed with clomiphene. This is a direct consequence of removing the estrogenic zuclomiphene isomer from the equation.

Meta-analytic reviews of serm therapy in male hypogonadism, which include enclomiphene data, consistently show testosterone improvements that are statistically comparable to testosterone gel in some endpoints, while preserving the endogenous production pathway. That preservation has significant downstream implications, particularly for fertility.

Researchers examining hormone research protocols have noted that enclomiphene's hormonal effects also demonstrate a notable persistence after discontinuation. Unlike exogenous testosterone, which suppresses the HPG axis and leads to rapid post-cessation decline, enclomiphene appears to recalibrate the axis rather than override it. This post-treatment persistence is a subject of active investigation.

Spermatogenesis: A Key Differentiator from TRT

Exogenous testosterone replacement therapy reliably suppresses LH and FSH, which in turn suppresses spermatogenesis. For men in whom fertility preservation is a research or clinical consideration, this represents a meaningful limitation of TRT as a comparator.

Enclomiphene, by stimulating FSH rather than replacing testosterone exogenously, supports continued spermatogenic signaling. Multiple studies have documented improvements in sperm concentration, motility, and morphology in men treated with enclomiphene, outcomes that stand in direct contrast to TRT's suppressive effects on semen parameters.

This distinction is central to understanding why enclomiphene in male endocrine research occupies a unique position relative to both clomiphene and testosterone-based interventions. For broader context on how signaling compounds interact with receptor systems, the literature on GPCR signaling provides useful mechanistic background.

Research Context, Regulatory Status, and 2026 Outlook

Research Context, Regulatory Status, and 2026 Outlook

Enclomiphene's regulatory history is instructive. The compound advanced through FDA Investigational New Drug (IND) processes with a specific focus on secondary hypogonadism, and early Phase II and Phase III data were sufficiently promising to attract significant interest. However, as of 2026, enclomiphene has not received formal approval for hypogonadism or testosterone support from any major regulatory body.

The 2026 British Society of Sexual Medicine (BSSM) position statement acknowledges enclomiphene among emerging options in the male hypogonadism landscape while stopping short of recommending it as a standard-of-care therapy. This reflects the current evidence gap: strong mechanistic rationale and encouraging trial data, but an incomplete formal approval pathway.

In practical research settings, enclomiphene is being studied with the following considerations in mind:

Research Variable Enclomiphene Profile
Isomer composition Pure trans-isomer only
Primary receptor action Estrogen receptor antagonist (hypothalamus)
LH/FSH effect Stimulatory
Estradiol impact Lower than clomiphene
Spermatogenesis Preserved or improved
Post-discontinuation persistence Documented in multiple studies
Regulatory status (2026) Investigational; no formal approval

Analysts tracking the male hormone therapeutics space in 2026 view enclomiphene as a compound with a credible path toward eventual approval, though timelines remain speculative. The compound's clean isomer profile continues to generate interest among researchers working across hormone research domains.

For those studying peptide and hormone interactions more broadly, related work on compounds like the IPA Sermorelin stack and Tesamorelin combined with Ipamorelin illustrates how upstream signaling modulators are being evaluated across multiple endocrine axes simultaneously.

Safety Profile Relative to Clomiphene and TRT

Enclomiphene's safety advantages over clomiphene are largely attributable to the absence of zuclomiphene. Fewer estrogen-related adverse effects, including reduced rates of mood changes and visual disturbances, have been reported in enclomiphene-specific trials compared to racemic clomiphene data.

Compared to TRT, enclomiphene carries a different risk profile rather than a uniformly safer one. It does not suppress the HPG axis, avoids the erythrocytosis risk associated with exogenous androgens, and does not impair fertility. However, it requires a functioning pituitary-gonadal axis to produce its effects, limiting its utility in primary hypogonadism research models.

Conclusion

Enclomiphene in male endocrine research represents a meaningful advance in the precision with which scientists can probe LH, FSH, and testosterone signaling without clomiphene's mixed isomers introducing confounding estrogenic variables. Its mechanism is well-characterized, its hormonal outcomes are reproducible, and its fertility-preserving profile distinguishes it clearly from exogenous testosterone approaches.

Actionable next steps for researchers and practitioners:

  1. Differentiate clearly between clomiphene and enclomiphene when reviewing or designing studies, the isomer distinction is not interchangeable.
  2. Monitor the full hormonal panel, LH, FSH, total testosterone, and estradiol, to capture enclomiphene's selective signaling profile accurately.
  3. Track post-discontinuation data as a distinct research endpoint, given evidence of HPG axis persistence.
  4. Follow regulatory developments closely; the 2026 landscape suggests the formal approval question remains open and consequential.
  5. Contextualize within broader endocrine research by cross-referencing findings with related signaling pathways and compound interactions.

The compound's selective isomer profile is not merely a chemical footnote, it is the foundation of its research value.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/enclomiphene-in-male-endocrine-research-lh-fsh-and-testosterone-signaling-withou.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-21 13:03:432026-08-21 13:03:43Enclomiphene in Male Endocrine Research: LH, FSH, and Testosterone Signaling Without Clomiphene’s Mixed Isomers
Page 1 of 212
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top