

Peptides and Polypeptides in Modern Pharmacology: How Research-Use Peptides Compare With Classic Drugs Like Prednisone and Amlodipine
More than 100 peptide-based drugs are currently approved for clinical use worldwide, yet most patients filling prescriptions for prednisone or amlodipine have never heard the word "peptide." That gap in awareness matters, because Peptides and Polypeptides in Modern Pharmacology: How Research-Use Peptides Compare With Classic Drugs Like Prednisone and Amlodipine represents one of the most consequential shifts in how scientists think about drug design, target selectivity, and safety profiles heading into the second half of the 2020s.
Key Takeaways
- Peptides are chains of amino acids that act primarily at receptor surfaces, while classic small-molecule drugs like prednisone and amlodipine bind inside enzyme or ion-channel pockets.
- Research-use peptides such as GLP-1 analogs, MOTS-c, and BPC-157 are studied for metabolic, inflammatory, and regenerative endpoints that overlap with, but are mechanistically distinct from, classic drug targets.
- Peptides generally offer higher target selectivity, which researchers associate with narrower off-target effect profiles compared with broad-acting corticosteroids or calcium channel blockers.
- Manufacturing peptides via solid-phase peptide synthesis (SPPS) is more complex and costly than classic synthetic chemistry, influencing both pricing and regulatory pathways.
- As of 2026, research-use peptides are not approved replacements for prescribed medications and must be handled under strict research-only protocols.
What Makes a Peptide Different From a Classic Drug
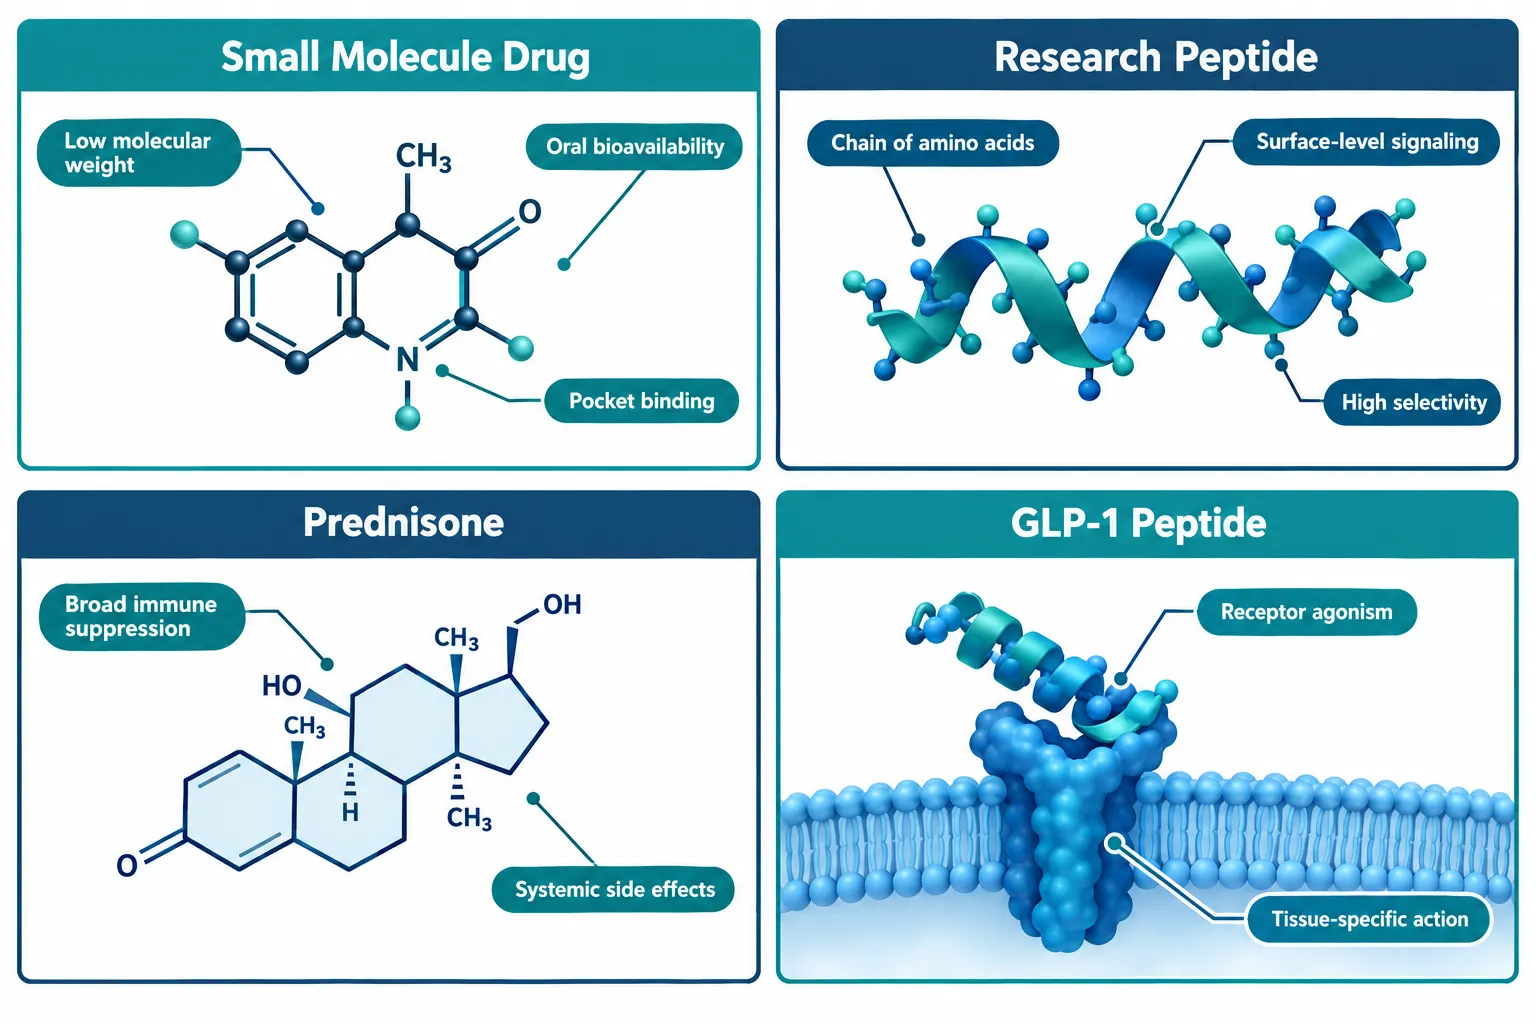
The FDA defines small-molecule drugs as compounds with a molecular weight generally below 500 daltons that can often be taken orally and absorbed intact. Prednisone, a corticosteroid, and amlodipine, a calcium channel blocker, are textbook examples. Both drugs work by fitting into a specific binding pocket, prednisone activates glucocorticoid receptors broadly across immune and metabolic tissues, while amlodipine blocks L-type calcium channels in vascular smooth muscle to lower blood pressure.
Peptides are short chains of amino acids linked by peptide bonds. They typically range from 2 to around 50 amino acids, placing them structurally between small molecules and full proteins. Rather than wedging into a pocket, most peptides bind to the external surface of receptors, triggering downstream signaling cascades with a level of specificity that small molecules often cannot match.
For a deeper look at how molecular size shapes these differences, the resource on peptides vs polypeptides and how molecular size and structure change research questions is worth reviewing.
"Selectivity is the central promise of peptide pharmacology, the ability to modulate a single pathway without the broad tissue footprint of a corticosteroid."
Key structural differences at a glance:
| Feature | Small Molecule (e.g., Prednisone) | Research Peptide (e.g., GLP-1) |
|---|---|---|
| Molecular weight | Under 500 Da | 500 Da to ~6,000 Da |
| Binding mode | Intracellular pocket | Receptor surface agonism |
| Oral bioavailability | Often high | Generally low (requires injection or nasal delivery) |
| Selectivity | Broad (multiple tissue types) | High (receptor-specific) |
| Manufacturing | Classic synthetic chemistry | Solid-phase peptide synthesis (SPPS) |
Mechanistic Contrasts: Surface Signaling vs Pocket Binding
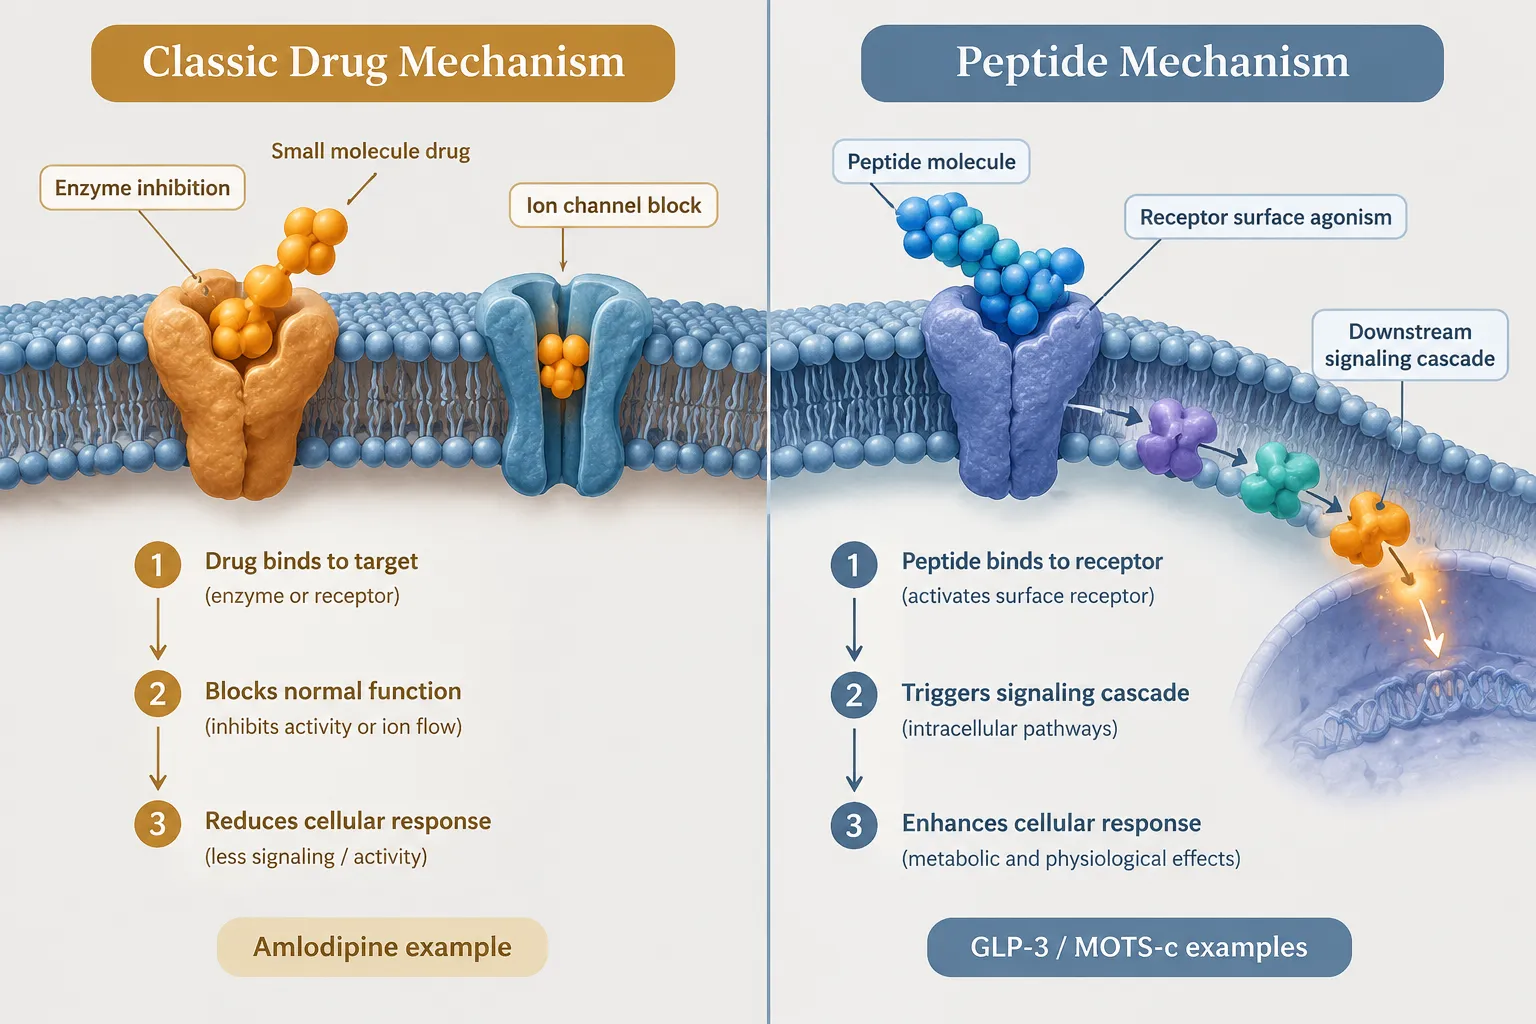
Understanding Peptides and Polypeptides in Modern Pharmacology: How Research-Use Peptides Compare With Classic Drugs Like Prednisone and Amlodipine requires a clear picture of how each drug class interacts with the body at the molecular level.
Prednisone enters cells and binds glucocorticoid receptors in the cytoplasm. That receptor-drug complex then travels to the nucleus and alters gene expression across dozens of cell types simultaneously. This mechanism explains both prednisone's power in suppressing inflammation and its well-documented side-effect profile, elevated blood sugar, bone density loss, and adrenal suppression, because the receptor it targets is expressed nearly everywhere.
Amlodipine works differently but is similarly broad. It blocks calcium entry into vascular smooth muscle cells and cardiac cells, reducing arterial resistance. Its selectivity is for a channel type, not a tissue, which is why it can cause peripheral edema and reflex tachycardia as off-target effects.
Research peptides like GLP-1 analogs, MOTS-c, and BPC-157 operate through surface receptor engagement:
- GLP-1 peptides bind GLP-1 receptors on pancreatic beta cells and gut enteroendocrine cells, stimulating insulin release in a glucose-dependent manner. The complete research guide for GLP-1, GLP-2, GLP-3, and growth hormone peptides covers these pathways in detail.
- MOTS-c is a mitochondria-derived peptide studied for its role in metabolic regulation and insulin sensitivity, explored further in research on MOTS-c mitochondrial signaling and metabolic research.
- BPC-157 is a synthetic peptide studied in tissue repair and inflammatory models, with a receptor profile still under active investigation.
Because these peptides act on specific receptor populations, researchers hypothesize that their off-target footprints may be narrower than those of prednisone or amlodipine, though this remains an area of active preclinical and translational study.
Manufacturing, Regulatory Status, and the Research-Use Framework
Manufacturing complexity is one reason Peptides and Polypeptides in Modern Pharmacology: How Research-Use Peptides Compare With Classic Drugs Like Prednisone and Amlodipine involves such different supply chains. Prednisone and amlodipine are synthesized through well-established organic chemistry routes that have been optimized over decades, making them inexpensive to produce at scale.
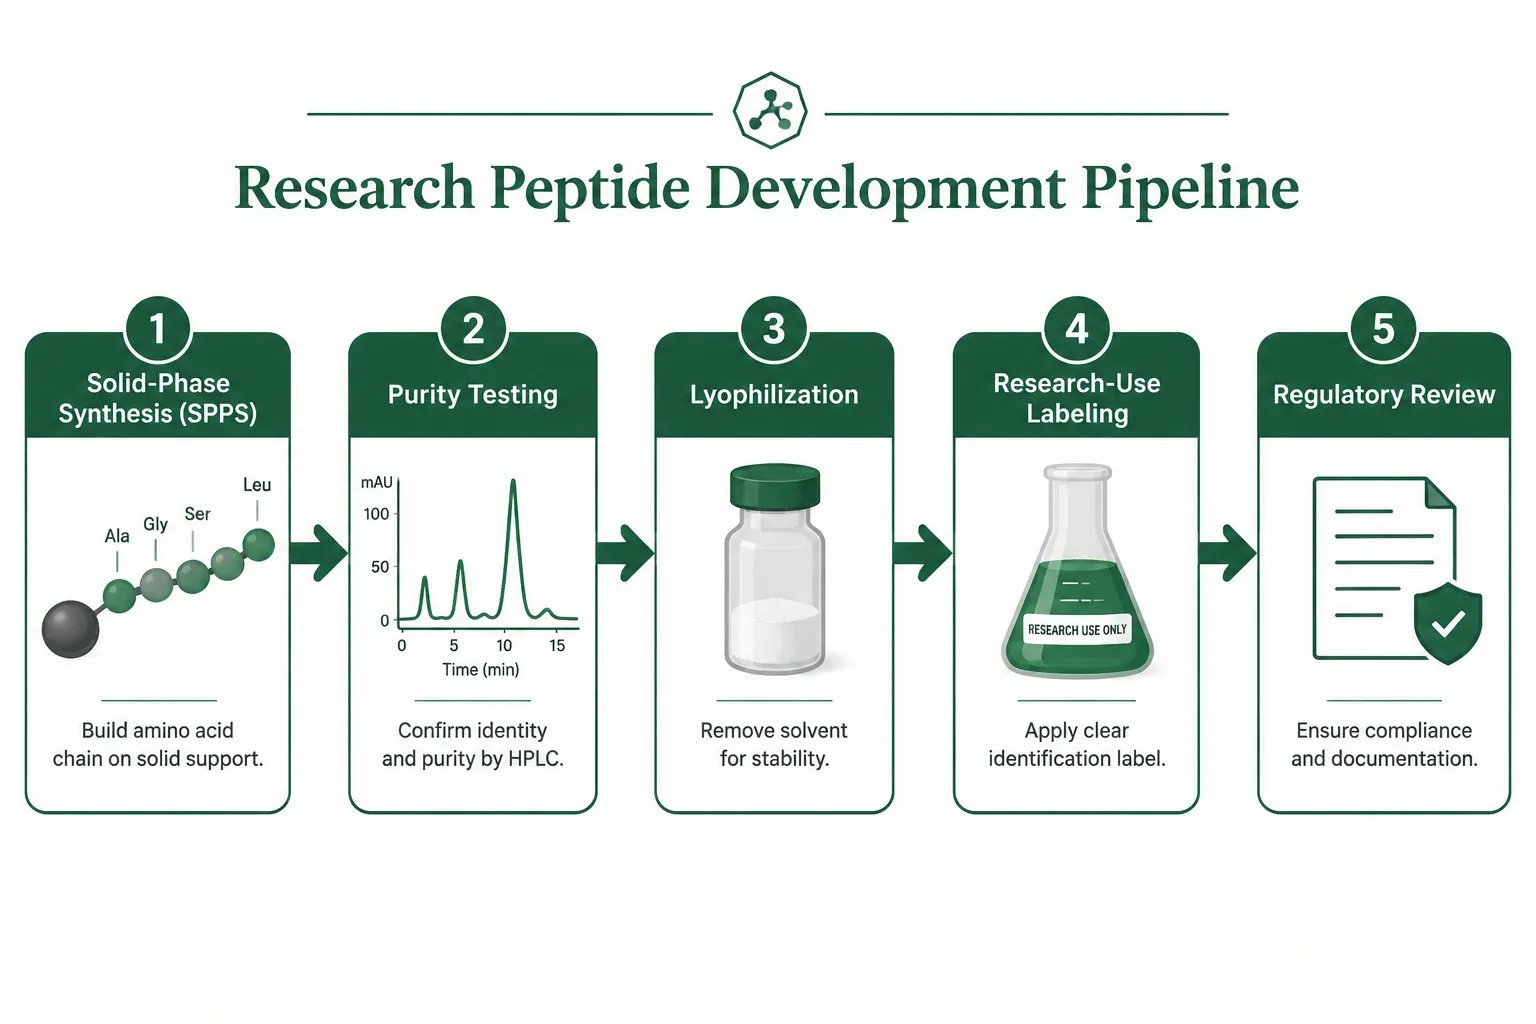
Peptides require solid-phase peptide synthesis (SPPS), a stepwise process that assembles amino acids one at a time on a resin scaffold. Each additional amino acid increases the risk of synthesis errors, racemization, and impurity formation. Post-synthesis purification, typically by high-performance liquid chromatography, adds further cost and complexity. Lyophilization (freeze-drying) is then used to stabilize the final product for storage and shipping.
Regulatory status in 2026 draws a sharp line between approved peptide drugs and research-use compounds:
- Approved peptide drugs (semaglutide, tirzepatide, tesa) have passed full FDA clinical trial requirements and carry approved indications.
- Research-use only (RUO) peptides, including GLP-3 analogs, MOTS-c, BPC-157, and Semax, are sold exclusively for in vitro and laboratory research. They are not approved for human administration, and as of mid-2026, the FDA has issued product-specific guidances tightening the compounding pathway for several peptide categories.
Labs sourcing these compounds need to understand reconstitution and dosing precision. Resources like the guide on essential tools and methods for accurate dosing and reconstitution in research provide practical frameworks for this work.
For researchers studying cardiometabolic endpoints, the same disease territory where amlodipine and prednisone are commonly prescribed, the article on polypeptide peptides in cardiometabolic models and how they differ from classic small-molecule drugs offers direct mechanistic comparisons.
Pipeline Trends and the Complementary Role of Peptides
Investment in peptide therapeutics has accelerated sharply since 2022, driven largely by the commercial success of GLP-1 receptor agonists. As of 2026, peptide-based compounds are entering clinical pipelines for oncology, cardiovascular disease, neuroinflammation, and metabolic syndrome, areas historically dominated by small molecules.
This does not mean peptides will replace drugs like prednisone or amlodipine in the near term. The two drug classes are increasingly viewed as complementary rather than competitive:
- Prednisone remains the standard of care for acute inflammatory flares where rapid, broad immune suppression is needed.
- Amlodipine remains a first-line antihypertensive with decades of safety data.
- Research peptides are being studied to address residual disease burden, improve metabolic co-morbidities, and potentially reduce the dose burden of classic drugs in combination protocols.
For labs exploring metabolic research specifically, the top 5 research peptides for metabolic health buyer's guide provides a current overview of the most studied compounds in this space.
Conclusion
The contrast between research-use peptides and classic drugs like prednisone and amlodipine is not simply a matter of novelty versus tradition. It reflects a fundamental difference in how each drug class engages biological systems, broad pocket-binding versus targeted surface signaling, systemic gene expression changes versus receptor-specific downstream cascades.
Actionable next steps for researchers and informed readers:
- Clarify regulatory status first. Before sourcing any peptide compound, confirm whether it carries RUO designation or clinical approval. These categories carry very different handling requirements in 2026.
- Map the mechanism to the research question. If a study endpoint involves inflammation or blood pressure, understanding how a peptide's receptor profile compares with that of prednisone or amlodipine will sharpen experimental design.
- Use validated reconstitution tools. Peptide potency is highly sensitive to preparation errors; use established dosing calculators and follow lyophilized storage protocols.
- Monitor the regulatory landscape. FDA product-specific guidances for compounded peptides are evolving rapidly; staying current protects both research integrity and compliance.
The broader story of Peptides and Polypeptides in Modern Pharmacology: How Research-Use Peptides Compare With Classic Drugs Like Prednisone and Amlodipine is still being written, but the mechanistic foundations are clear enough to guide rigorous, well-designed research today.


Leave a Reply
Want to join the discussion?Feel free to contribute!