CJC-1295 With DAC vs Without DAC: Which Research Formulation Fits Pulsatile or Sustained GH Experiments?
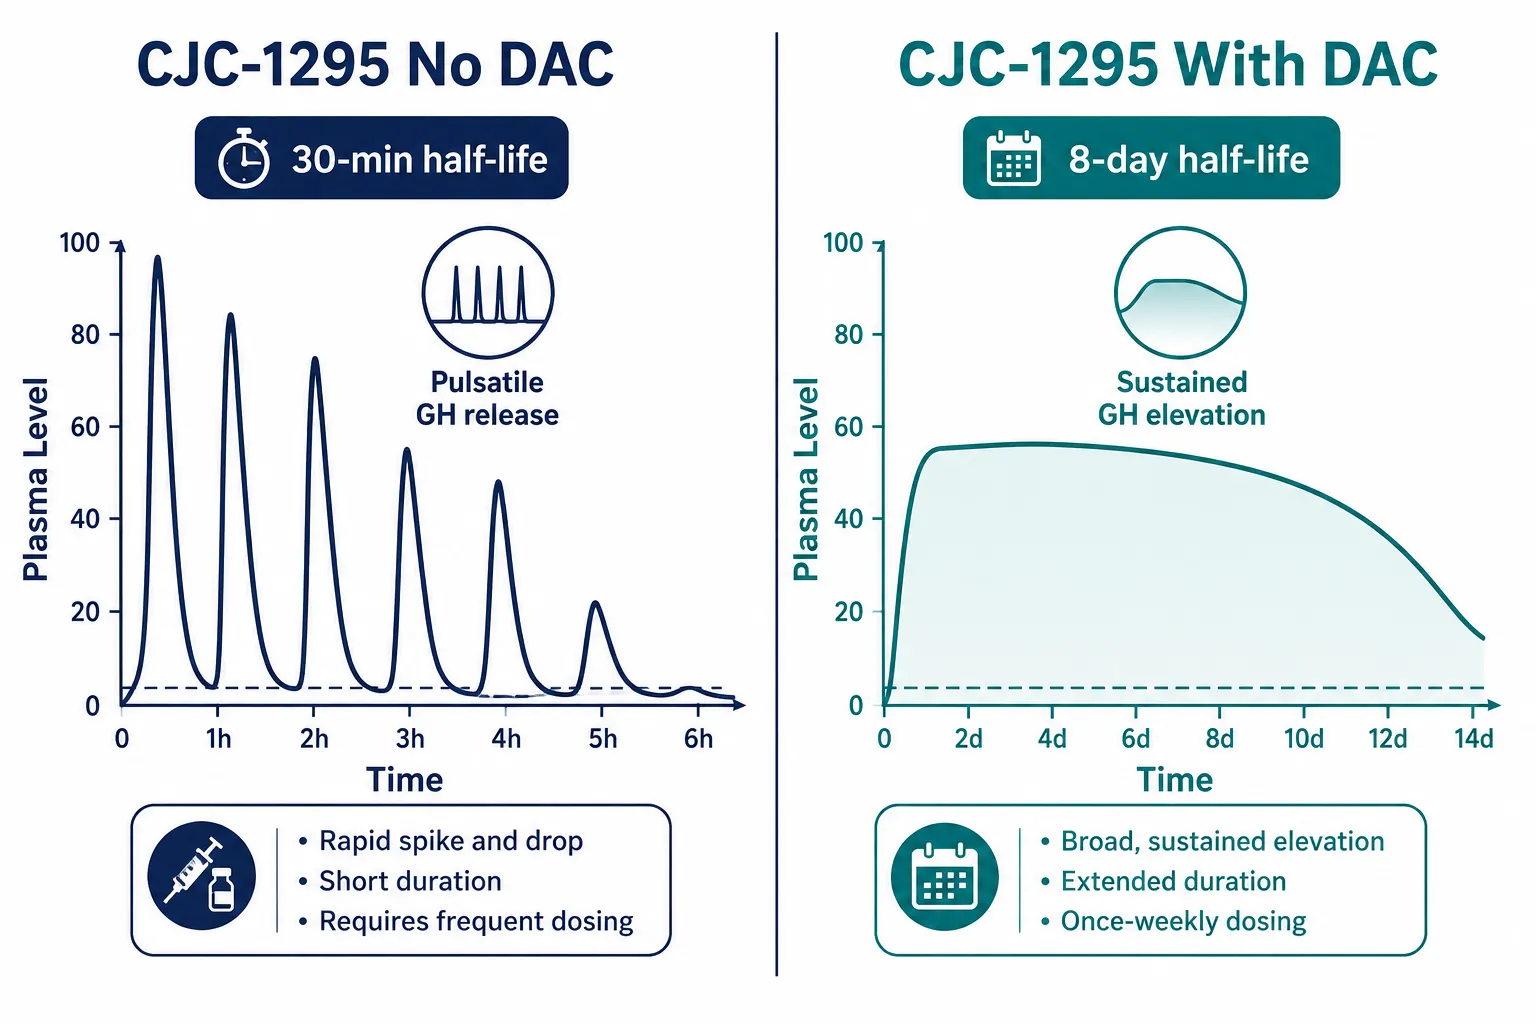
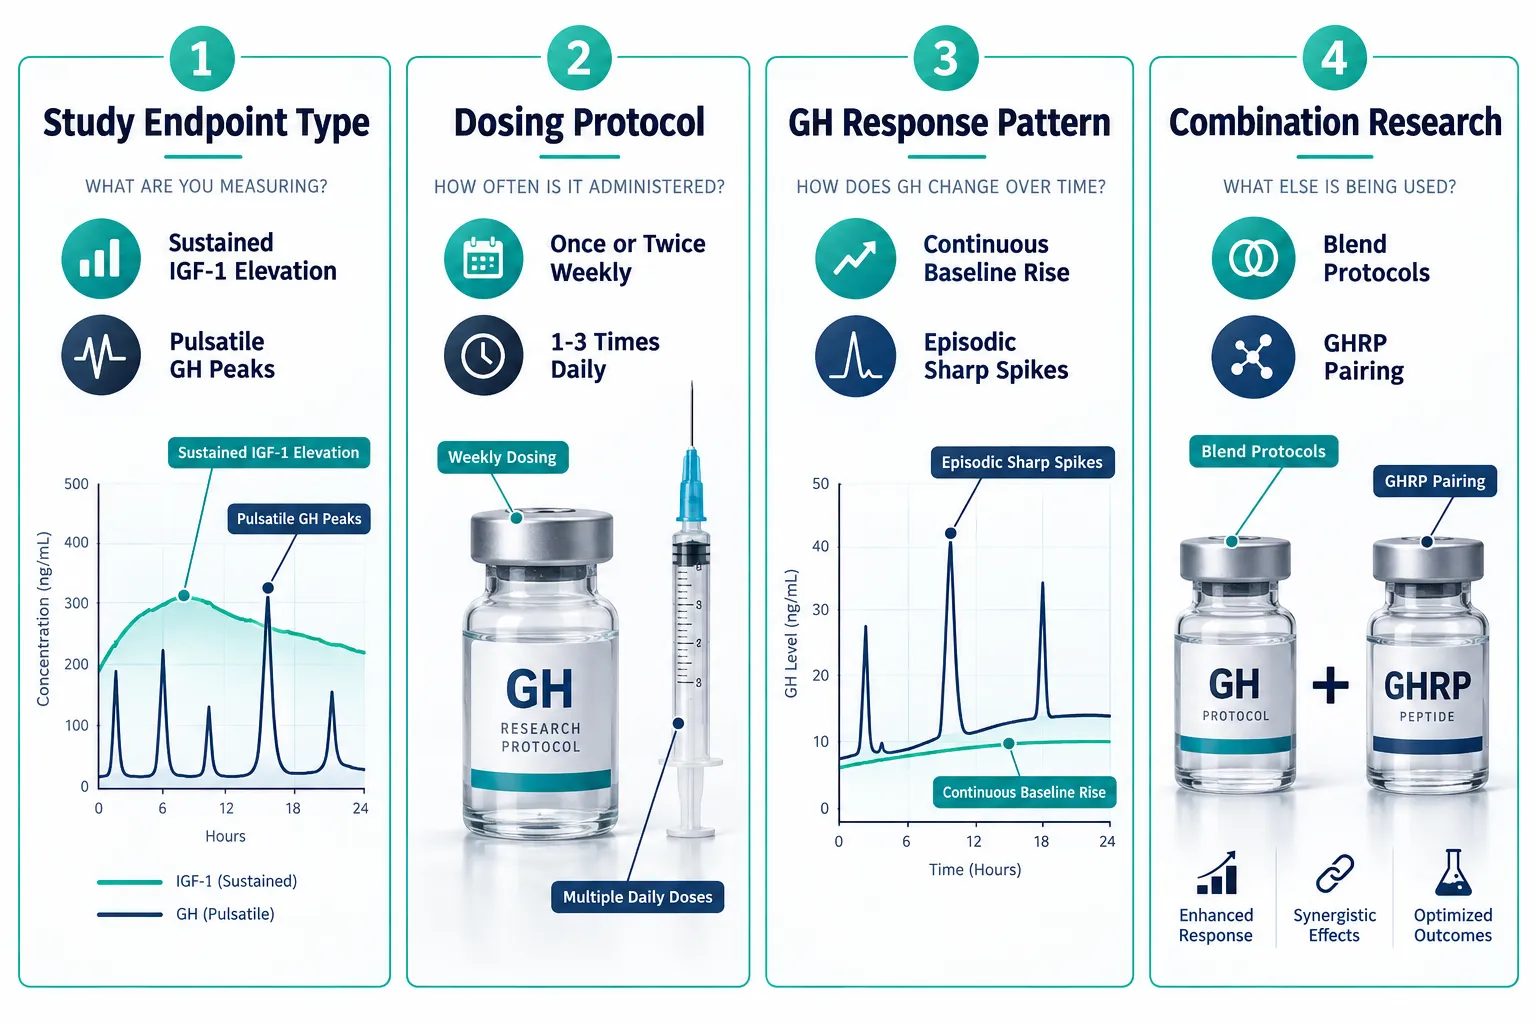
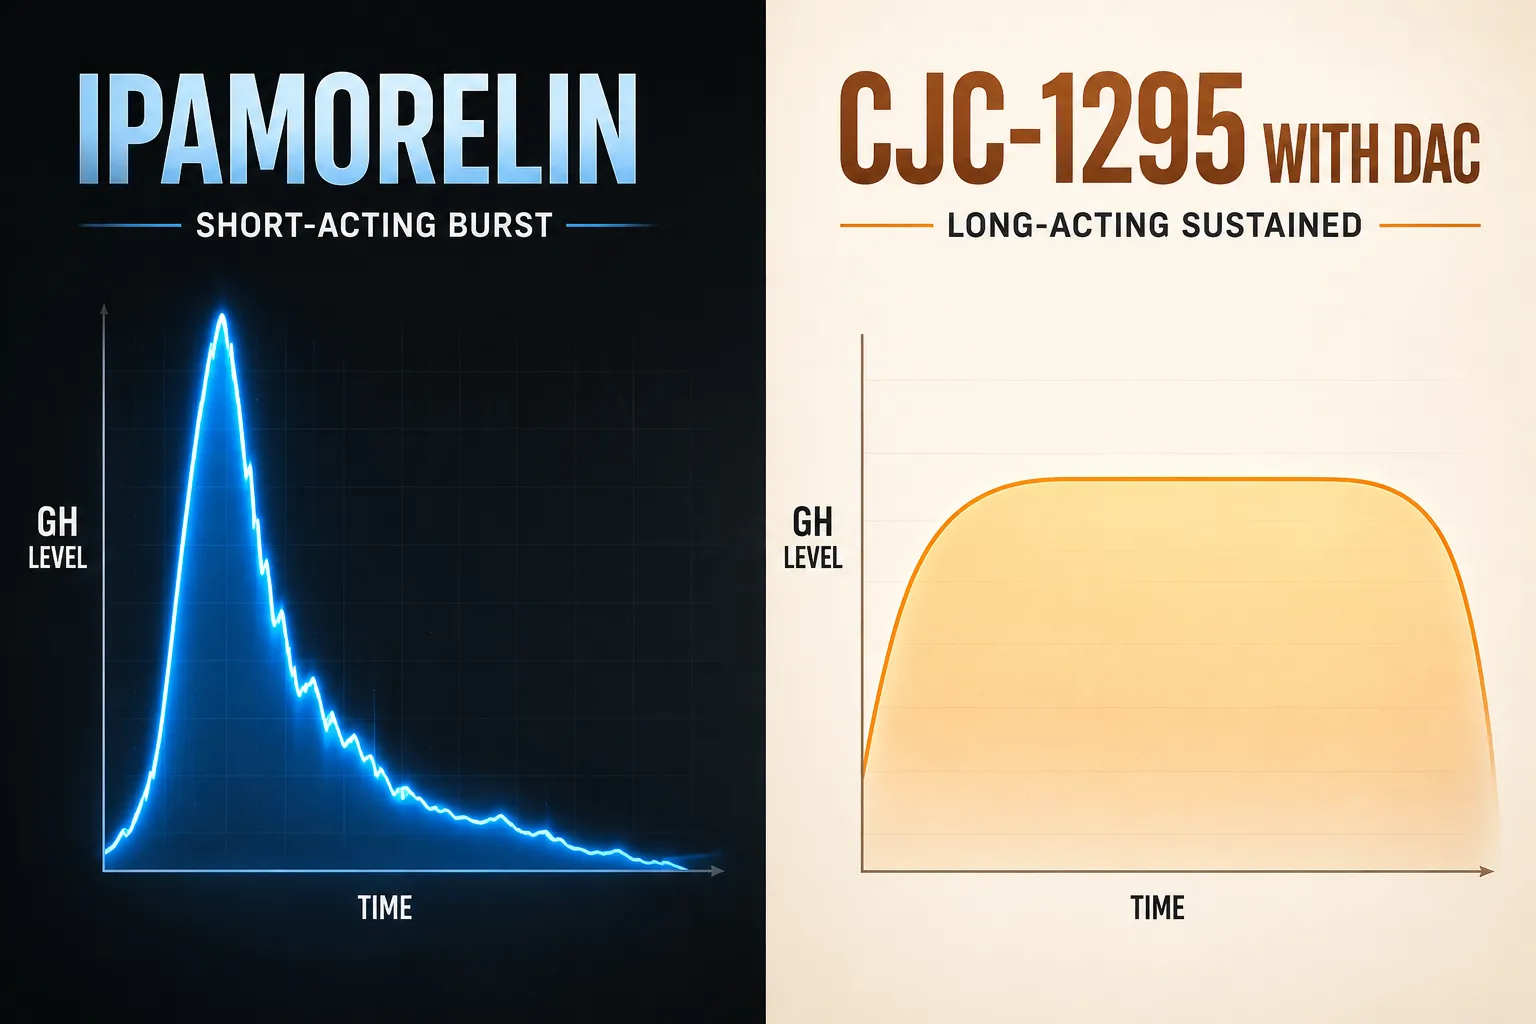
Growth hormone secretion is not a steady stream, it fires in discrete pulses, roughly 6 to 12 times per day in healthy adults. That biological reality makes the choice between CJC-1295 With DAC vs Without DAC: Which Research Formulation Fits Pulsatile or Sustained GH Experiments? far more consequential than a simple half-life comparison. The wrong formulation does not just alter kinetics; it can undermine the entire experimental design by masking pulse amplitude, drifting the baseline, or misaligning endpoint sampling windows.
Key Takeaways
- CJC-1295 without DAC (Mod GRF 1-29) produces discrete, timeable GH pulses ideal for pulsatile GH experiments and secretagogue synergy protocols.
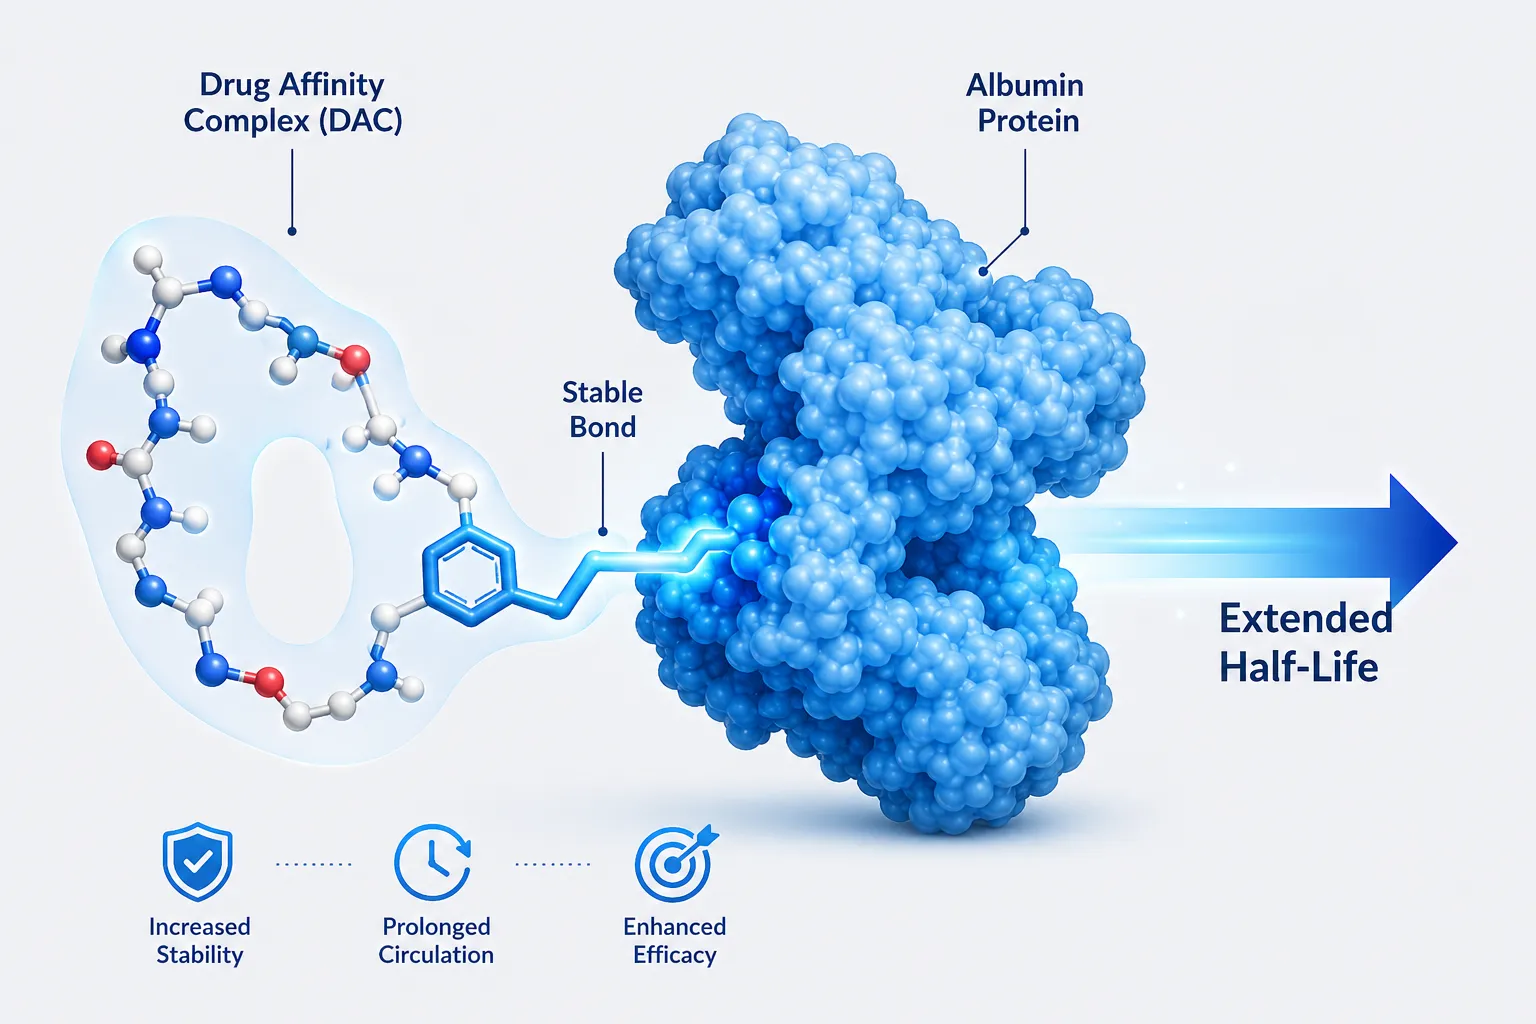
- CJC-1295 with DAC binds albumin to create a depot effect, delivering sustained GHRH receptor stimulation and multi-day IGF-1 elevation.
- The selection decision should rest on five variables: sampling density, receptor exposure pattern, baseline drift tolerance, pulse amplitude requirements, and endpoint timing.
- Combining CJC-1295 without DAC with a GHRP-class peptide amplifies pulse amplitude while preserving natural rhythm, the DAC form blunts this synergy.
- As of 2026, pharmacokinetic and hormonal data for both forms are well-established; clinical outcome evidence remains limited to investigational use.
The Selection Matrix: Five Variables That Actually Matter
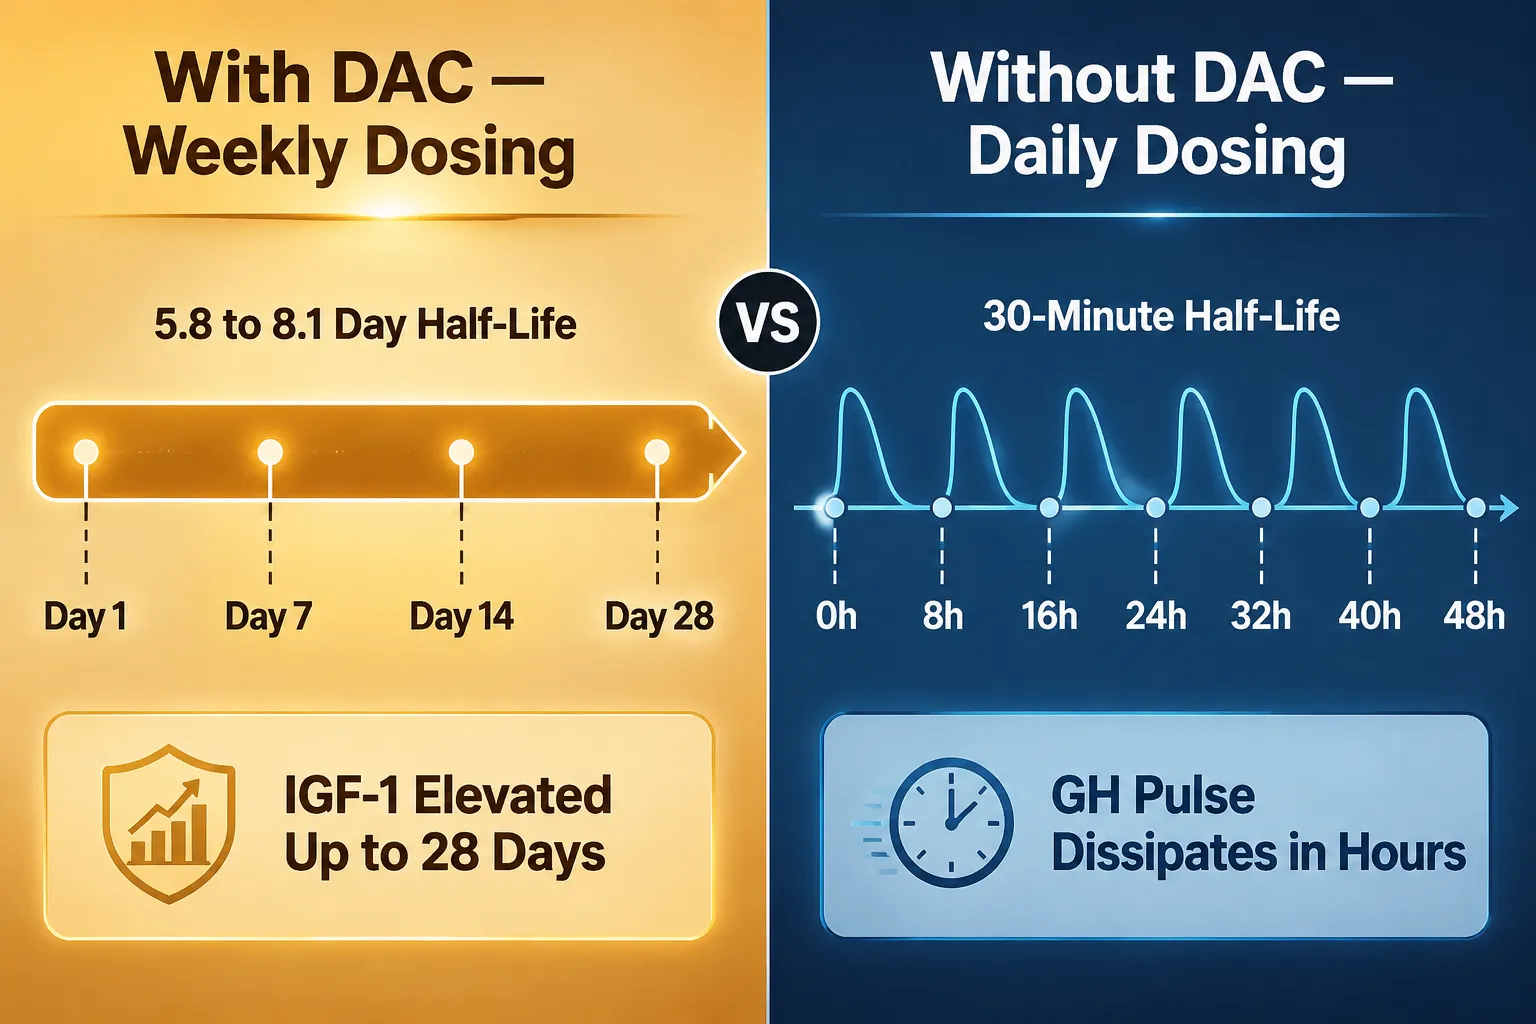
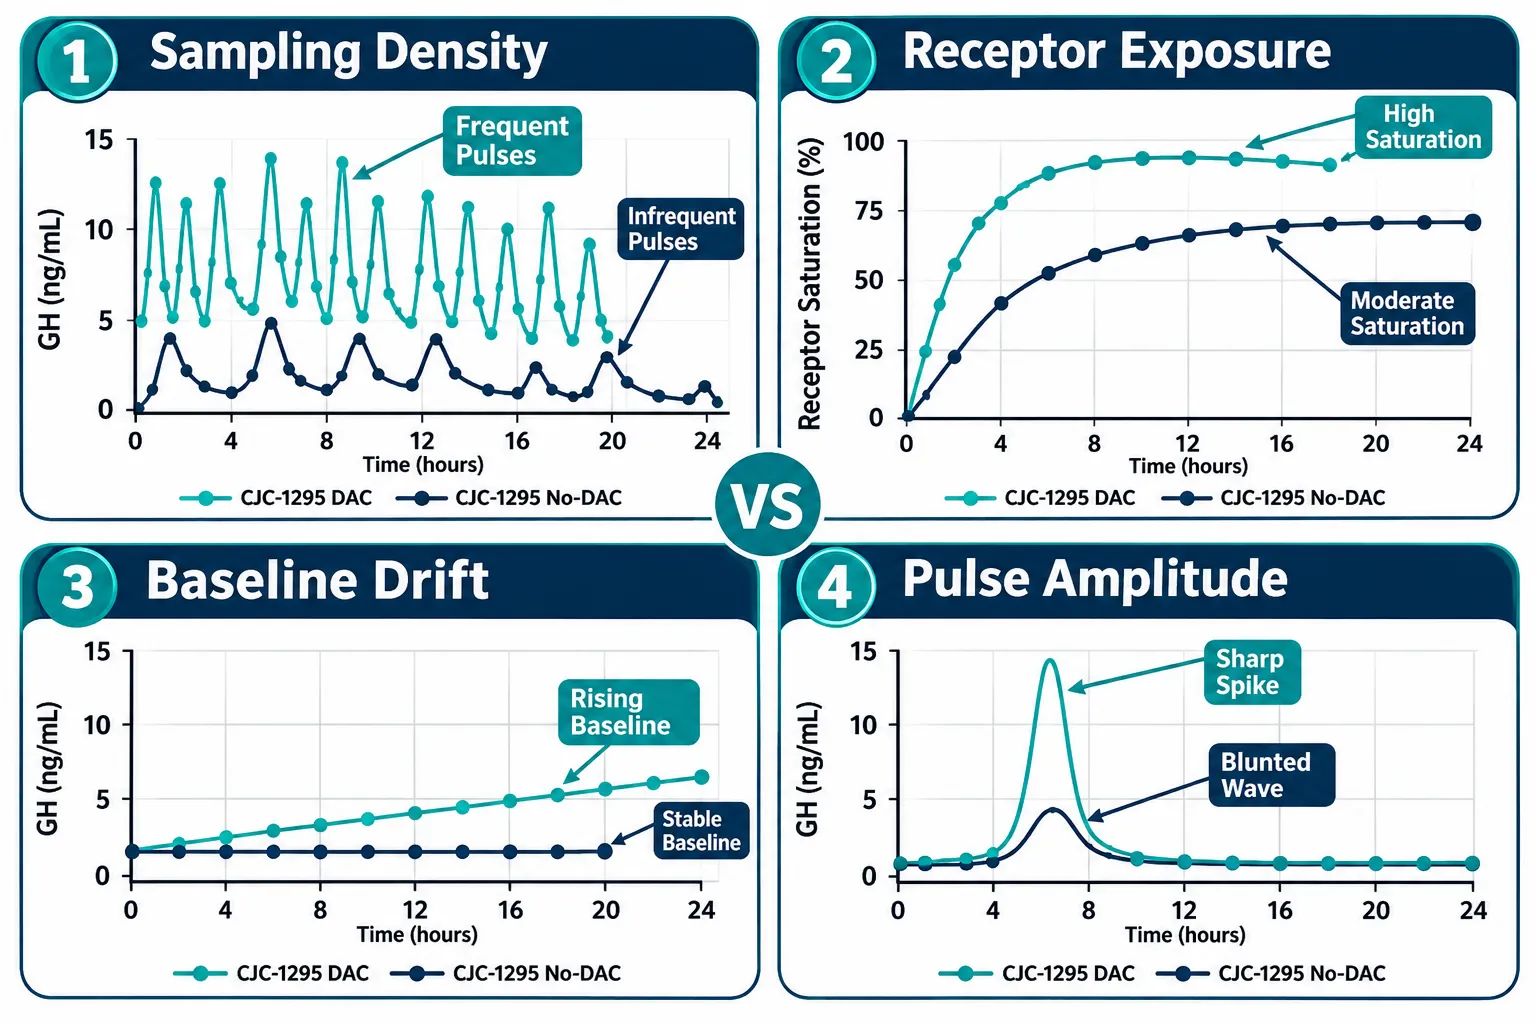
Choosing between the two formulations based on half-life alone, minutes versus roughly eight days, oversimplifies a decision that depends on experimental architecture. A more rigorous framework evaluates five variables.
1. Sampling Density
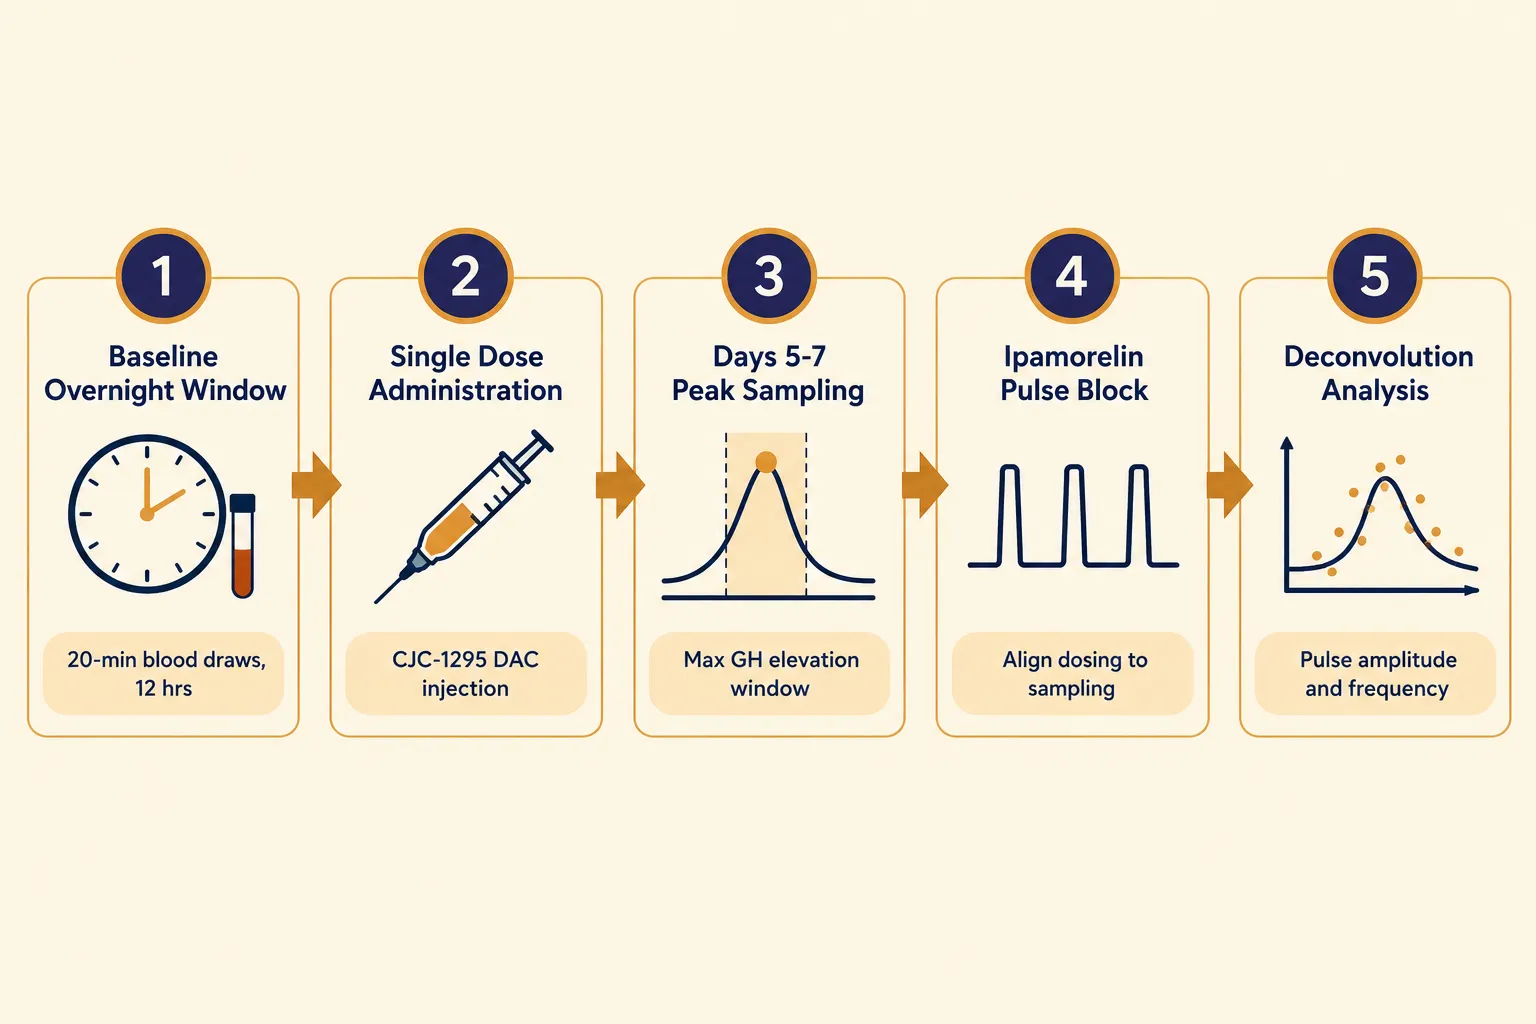
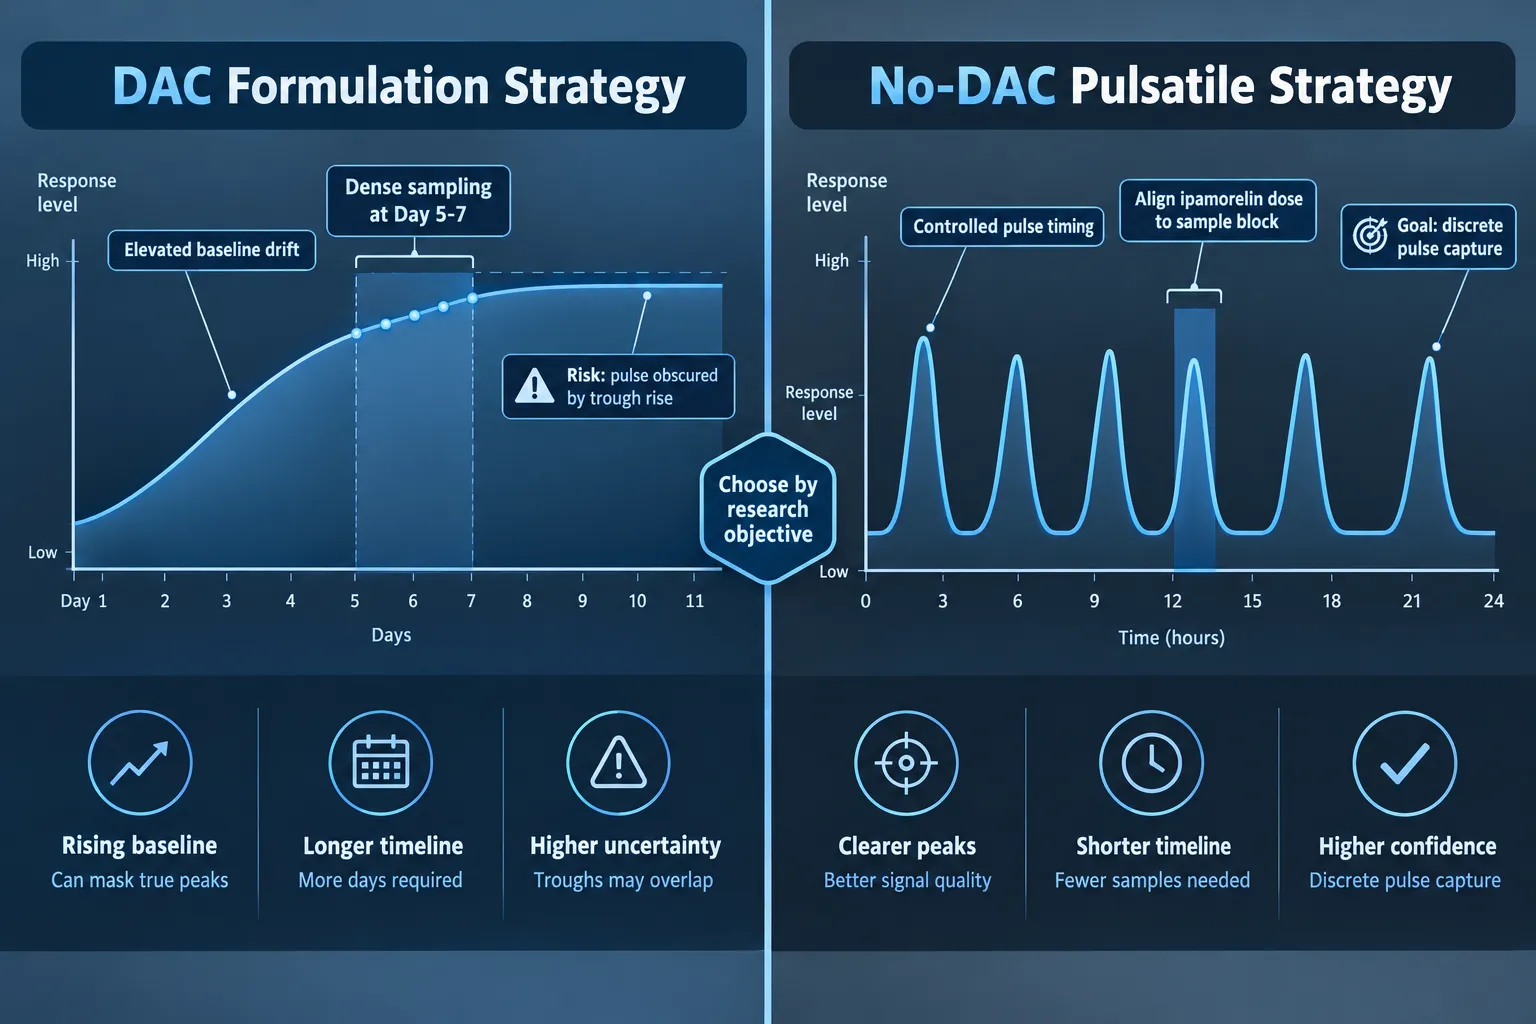
Experiments that require frequent blood draws, hourly or sub-hourly GH measurement, depend on predictable pulse timing. CJC-1295 without DAC allows researchers to trigger a pulse, then sample around it with precision. The DAC form creates a pharmacokinetic plateau that makes individual pulse identification nearly impossible within dense sampling windows.
2. Receptor Exposure Pattern
Continuous GHRH receptor stimulation from the DAC form risks desensitization over extended protocols. No-DAC administration preserves intermittent receptor "rest" periods, which mirrors physiological patterns and reduces tachyphylaxis risk in longer study designs.
3. Baseline Drift
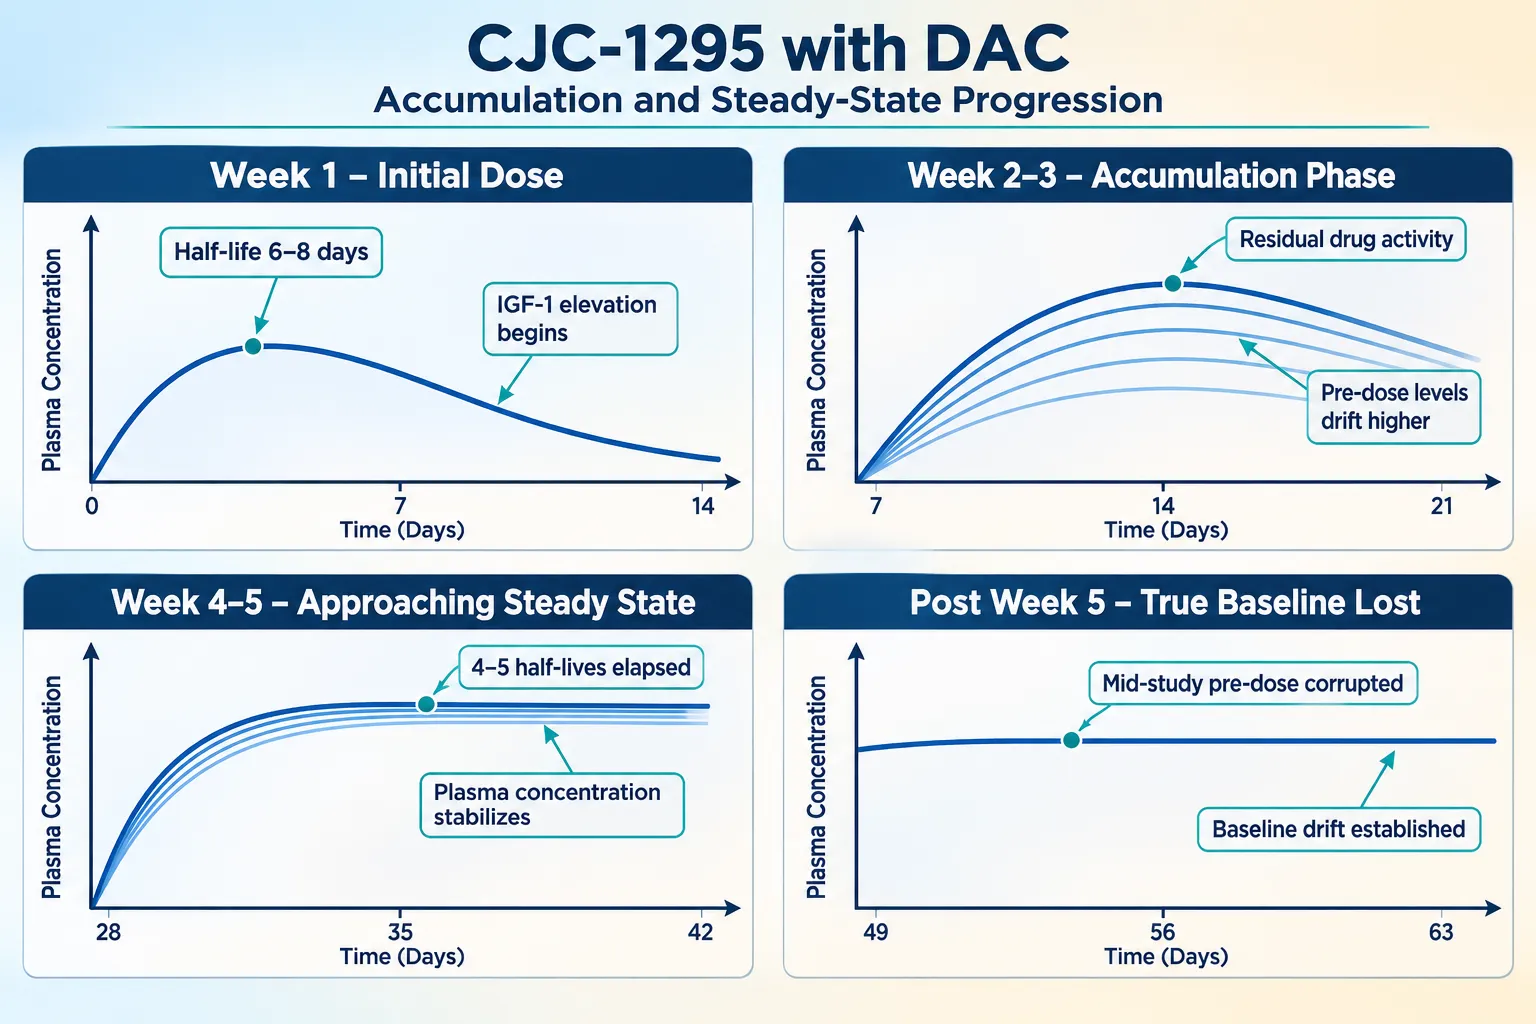
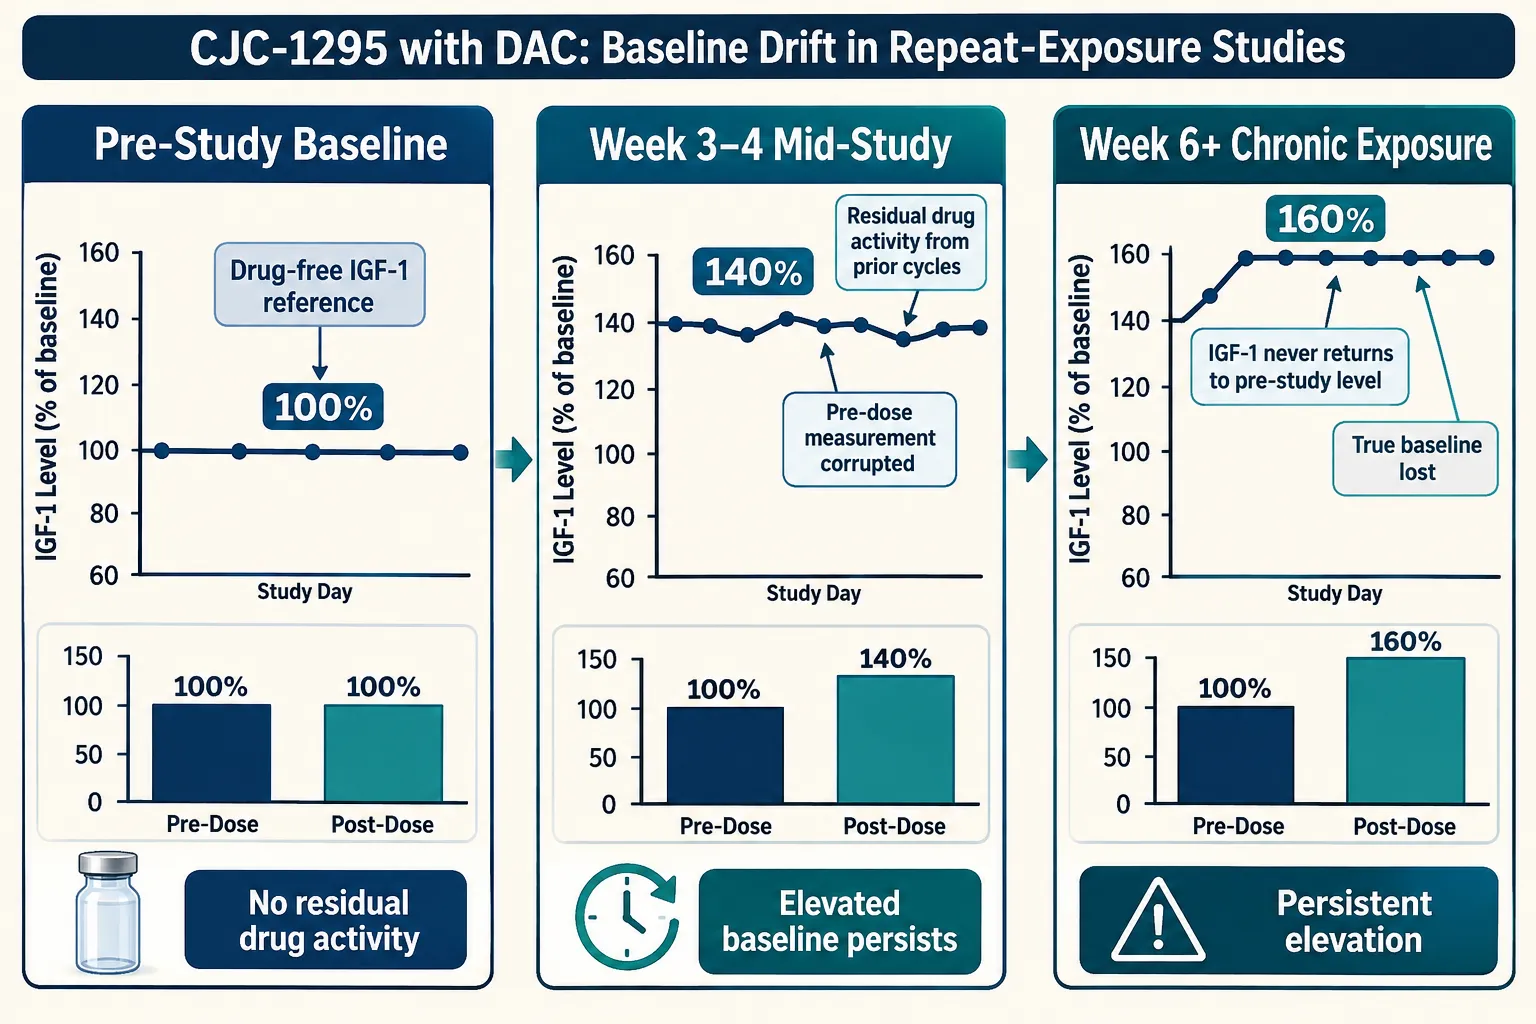
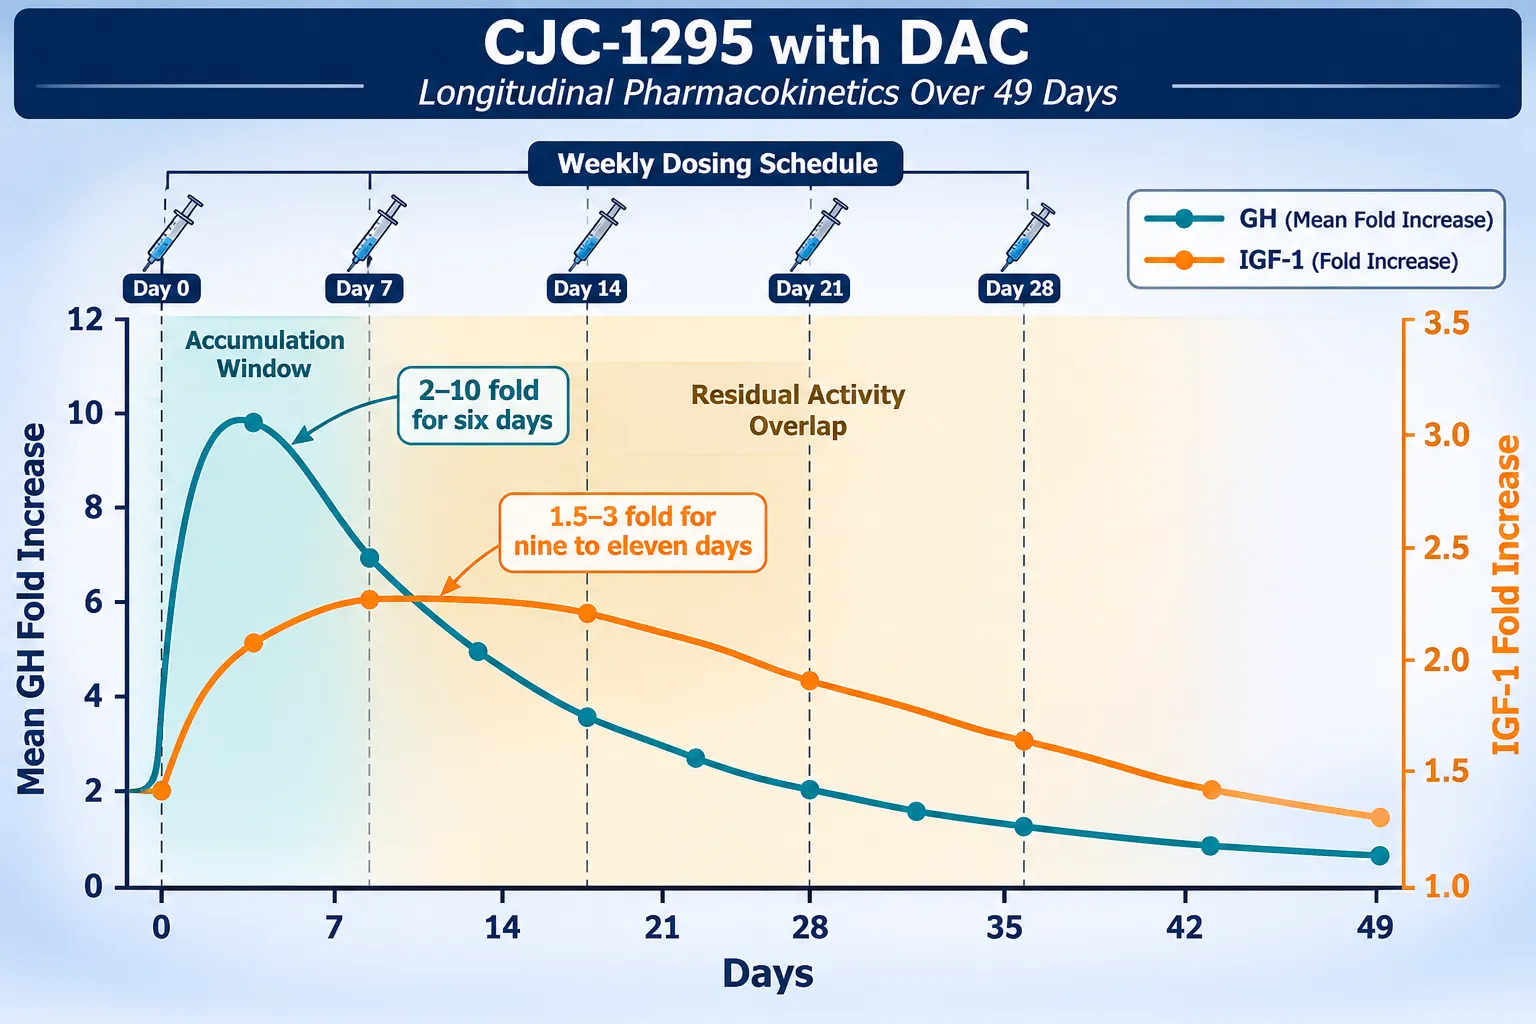
The DAC formulation raises the IGF-1 baseline progressively over the first several days and holds it elevated. This is valuable when the endpoint is sustained anabolic signaling, but it introduces confounding baseline drift in studies measuring acute hormonal responses.
4. Pulse Amplitude
Co-administration with a ghrelin mimetic or GHRP-class secretagogue produces the strongest GH pulse amplitude when the GHRH component (CJC-1295 without DAC) is timed precisely at the same injection moment. See CJC-1295 Ipamorelin dosage protocols for combination research frameworks. The DAC form cannot be "timed" to amplify a co-administered pulse in the same way.
5. Endpoint Timing
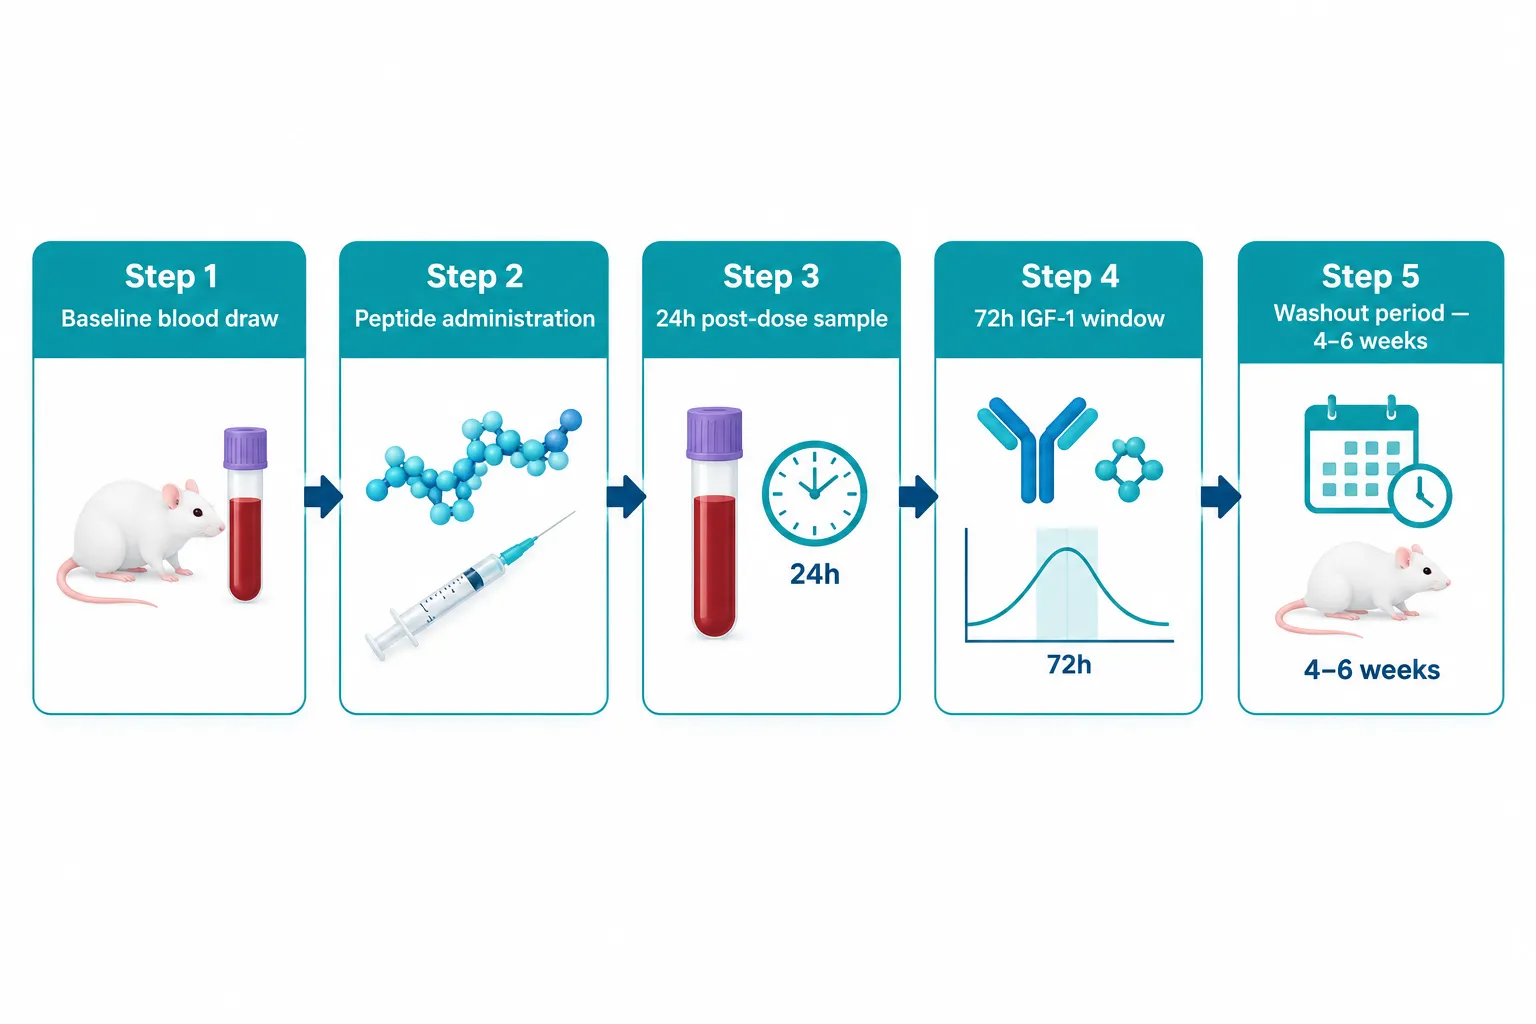
If the primary endpoint is measured at a fixed time point, 24, 48, or 72 hours post-administration, the DAC form is better suited because it maintains consistent circulating levels across that window. No-DAC experiments require careful alignment of sampling to the post-injection pulse window (typically 15 to 45 minutes).
| Variable | No-DAC (Mod GRF 1-29) | With DAC |
|---|---|---|
| Sampling window control | High | Low |
| Pulse amplitude precision | High | Blunted |
| Baseline stability | High | Progressive rise |
| IGF-1 elevation duration | Hours | Days |
| Receptor rest preservation | Yes | Limited |
Mechanistic Basis: How DAC Chemistry Changes the GH Profile
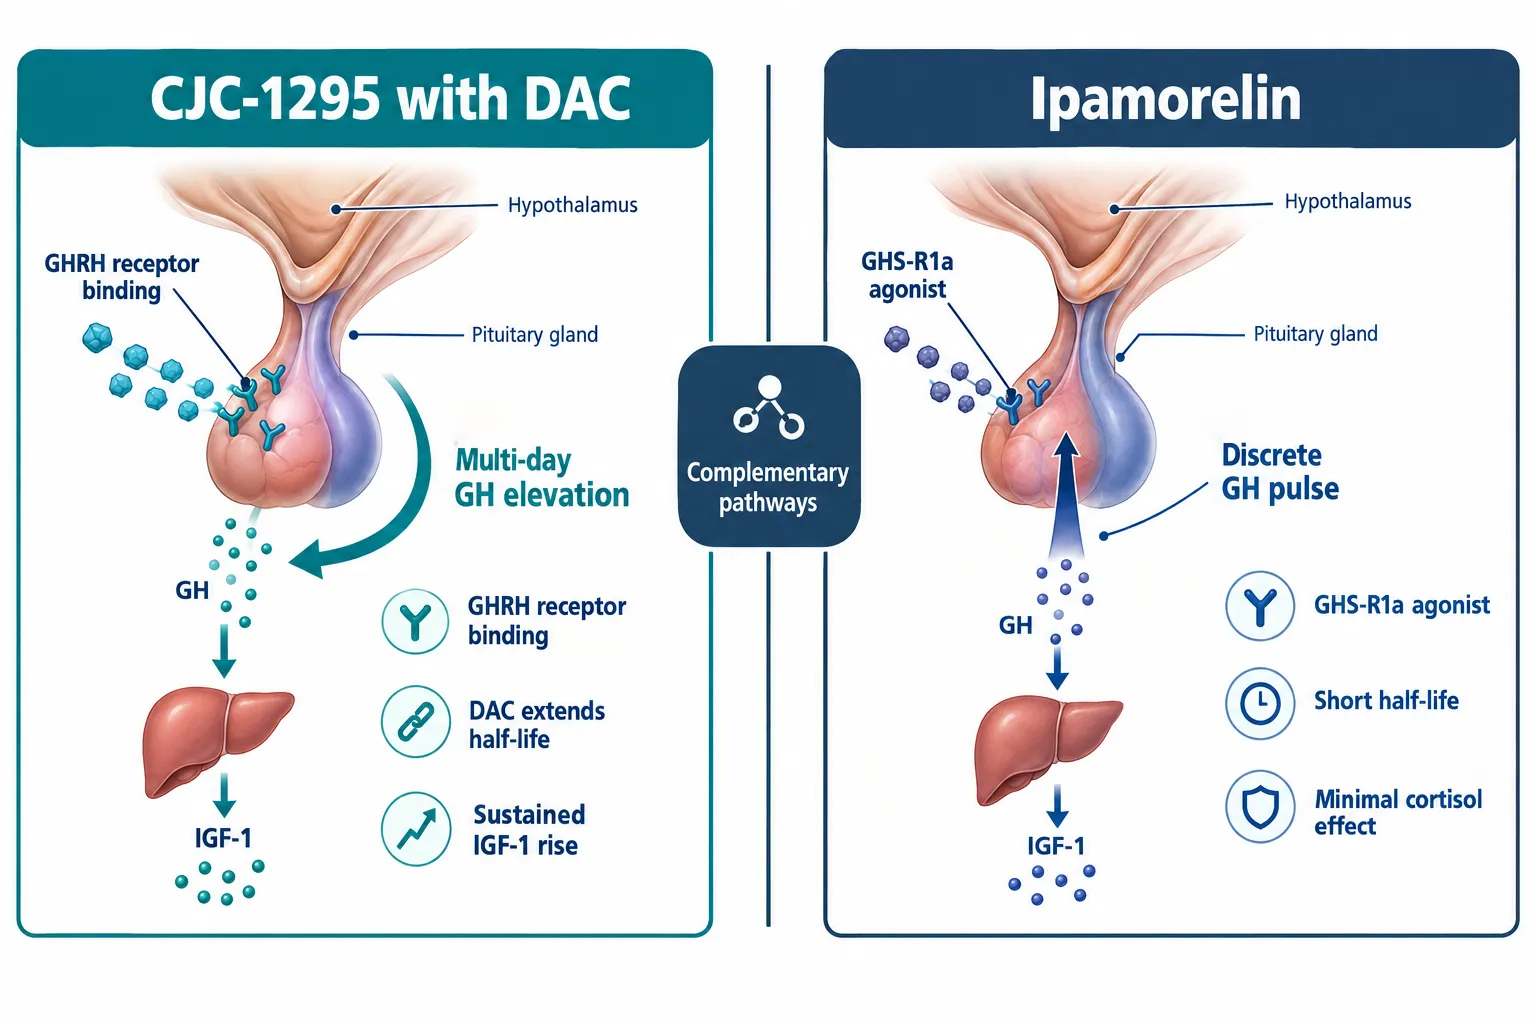
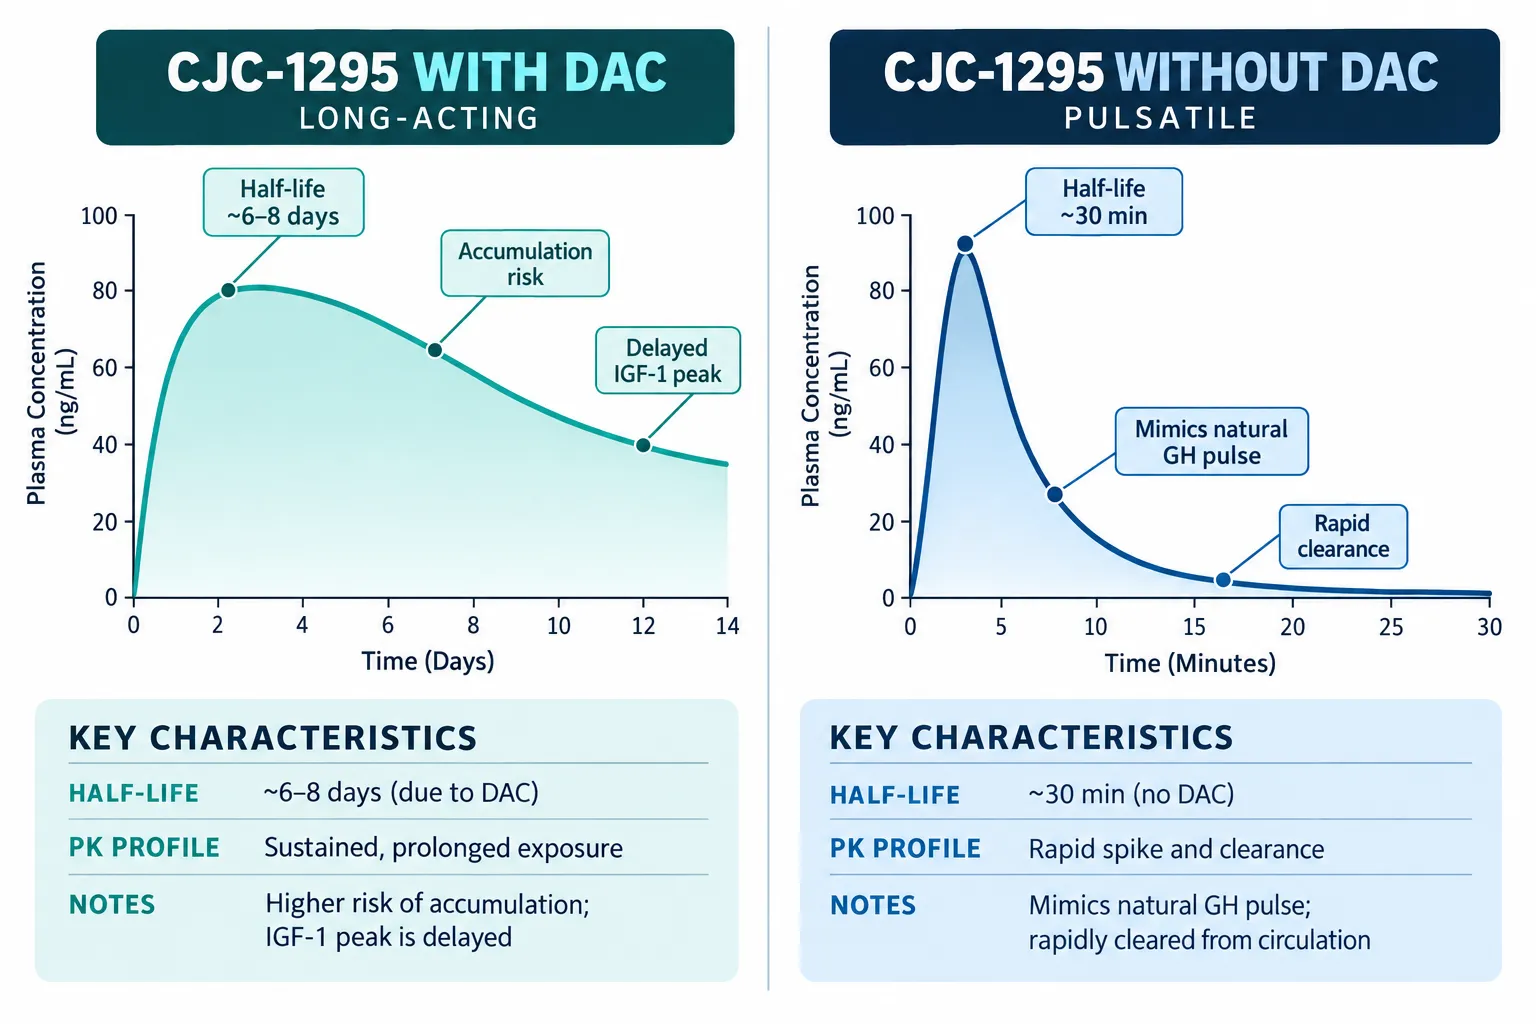
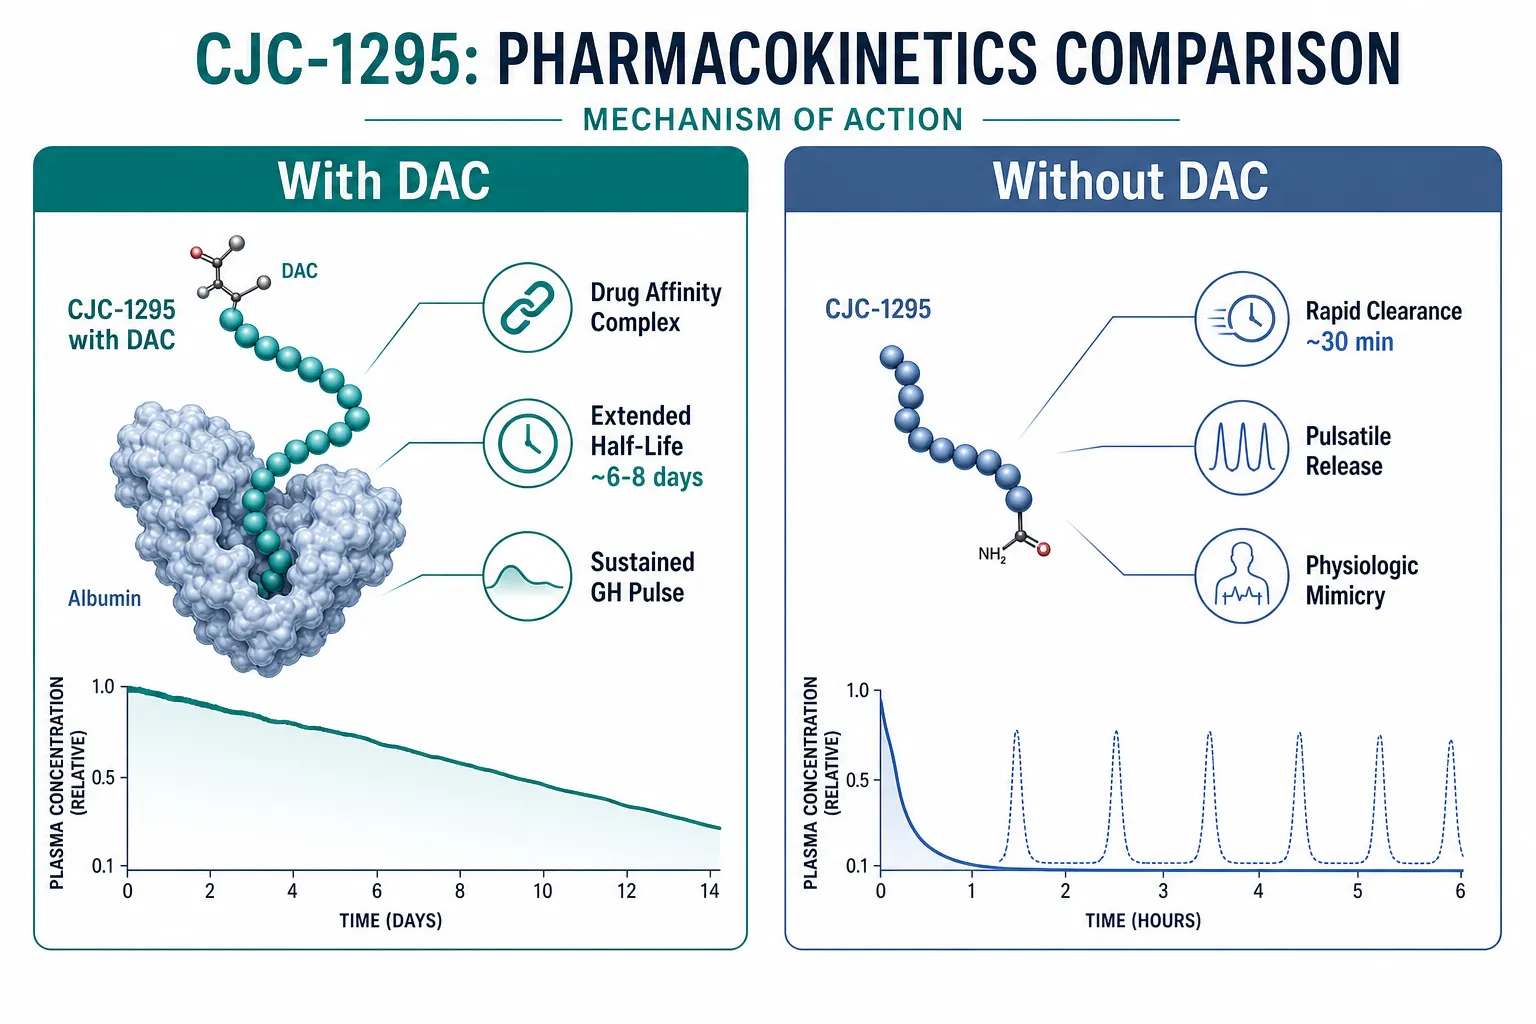
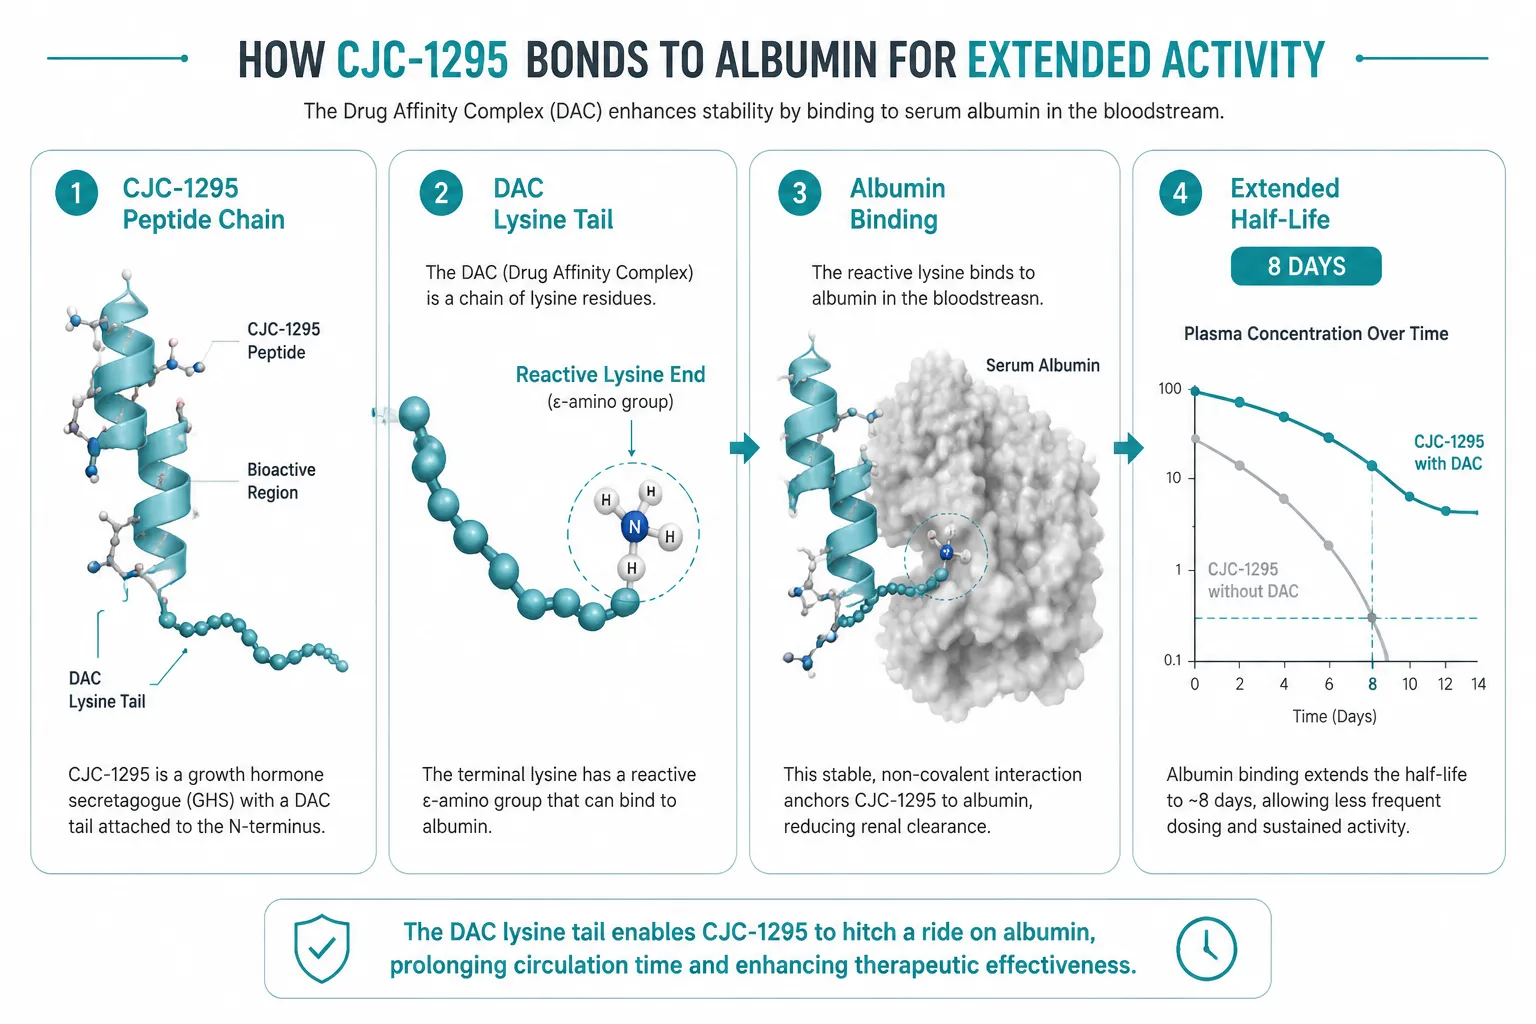
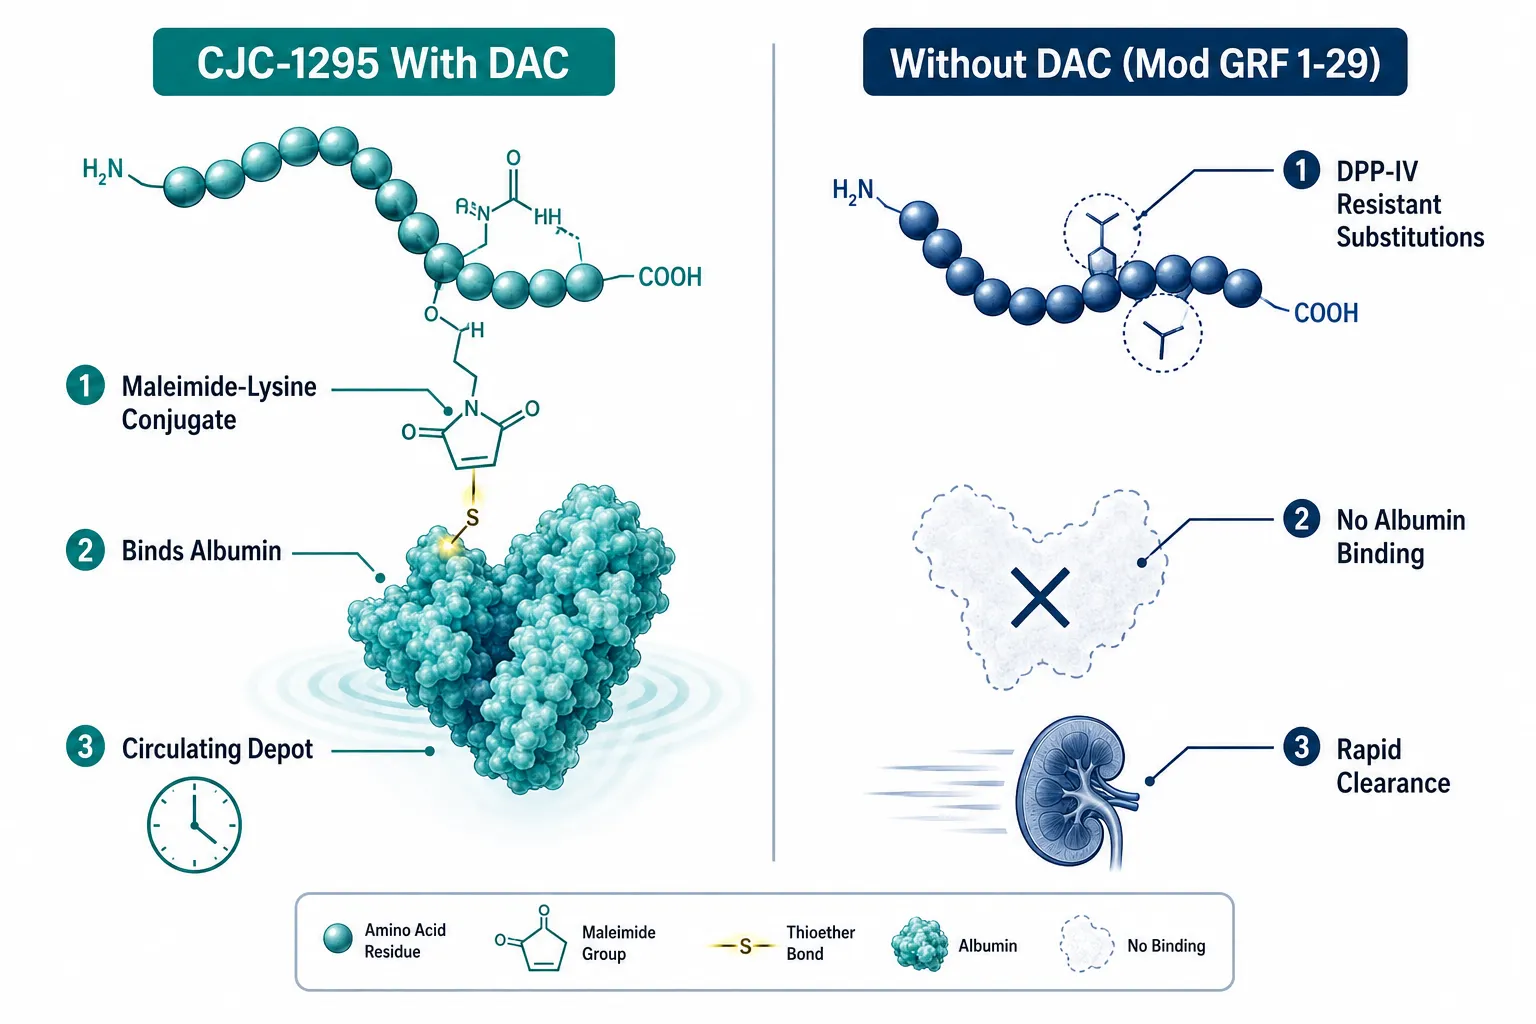
The Drug Affinity Complex (DAC) is a lysine-based side chain that binds reversibly to circulating albumin. This binding creates a molecular depot, the peptide is slowly released back into free circulation over days rather than being cleared within minutes.
The practical result is a GH and IGF-1 profile that resembles a prolonged plateau rather than a spike. Pituitary somatotrophs receive near-continuous GHRH receptor input, driving tonic growth hormone release and downstream hepatic IGF-1 production that remains elevated for the duration of the dosing interval.
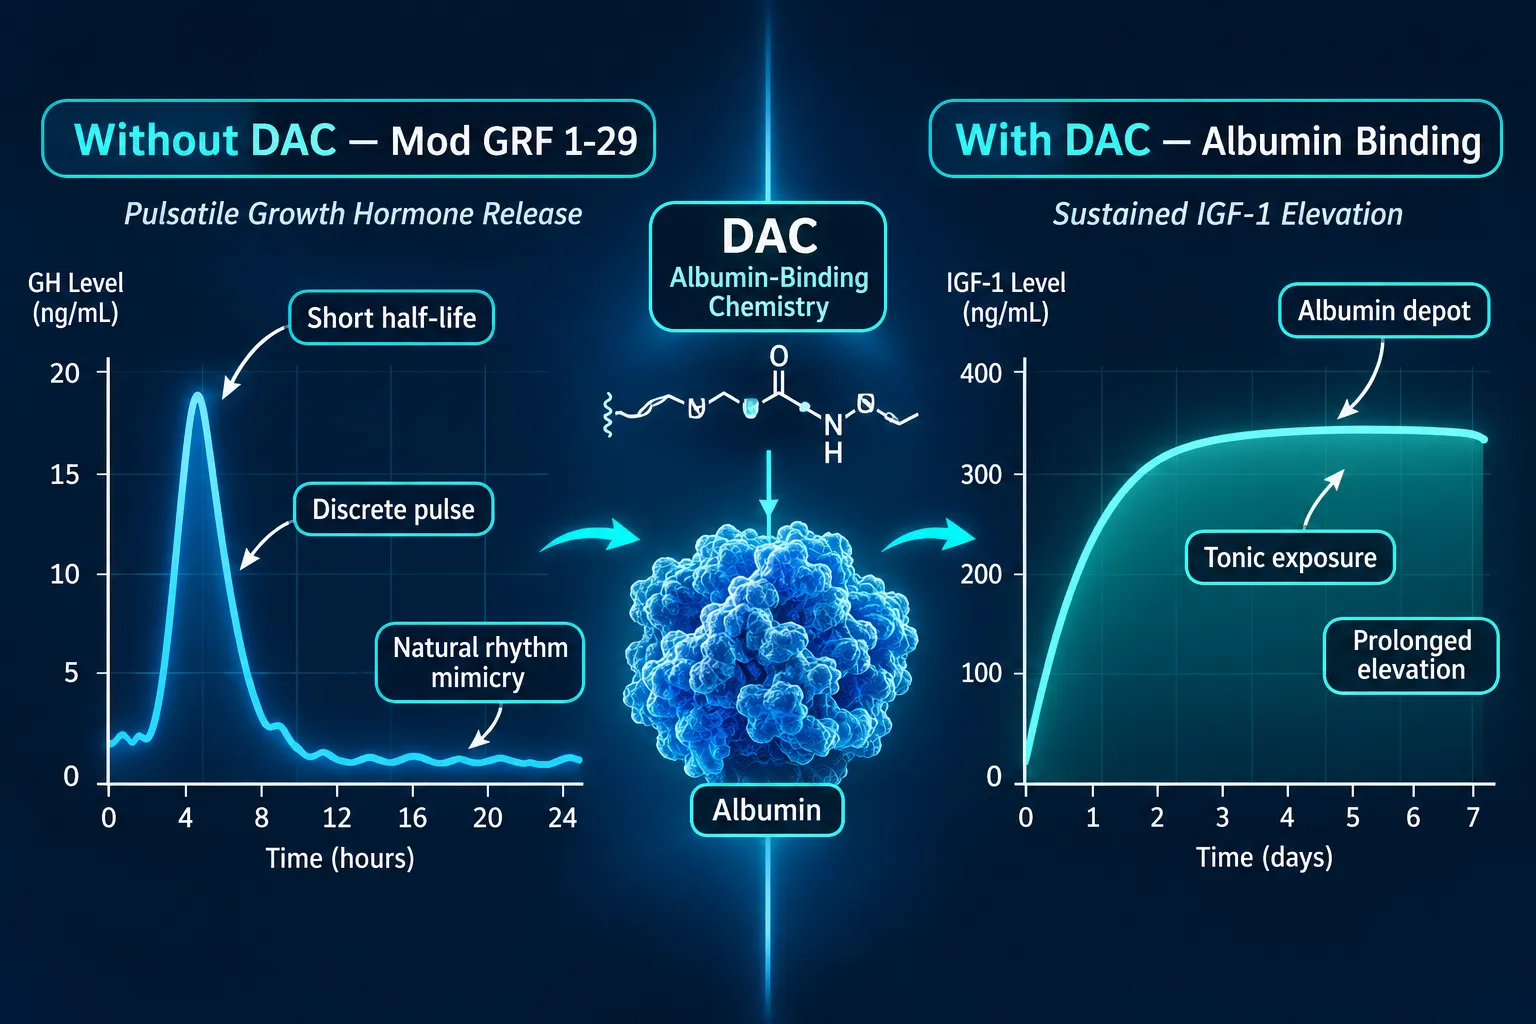
CJC-1295 without DAC lacks this modification. Its bioactive half-life, extended relative to native GHRH (1-44) by several protective amino acid substitutions but still measured in minutes to low single-digit hours, allows for a clean pulse-and-clear pharmacokinetic profile. Researchers studying growth hormone secretory dynamics, GH pulse frequency, or pituitary reserve benefit from this predictability.
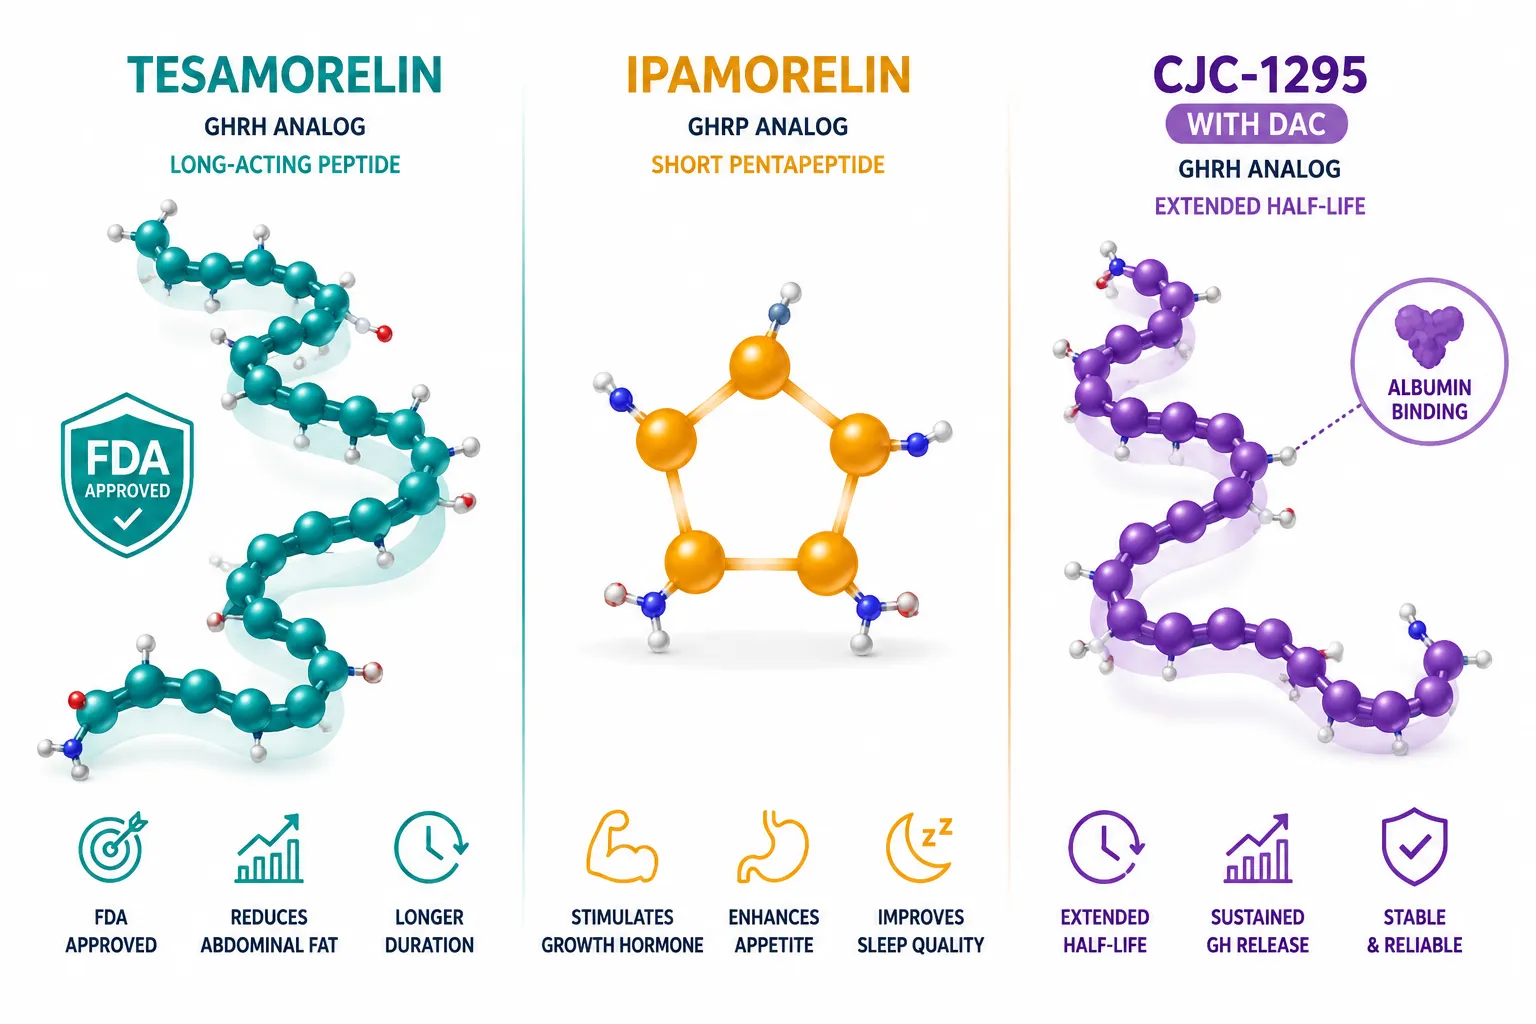
For experiments exploring visceral adipose reduction or metabolic endpoints with sustained hormonal exposure, the DAC form's depot behavior is a feature, not a limitation. For related metabolic research contexts, visceral fat research resources provide useful background on GH-axis involvement in adipose regulation. Similarly, researchers exploring related GHRH analogs may find Tesamorelin benefits data instructive as a comparator for sustained GHRH-axis stimulation.
Protocol Design Guidance for 2026 Research Applications
Matching formulation to experimental design is now the consensus standard in peptide research circles as of 2026.
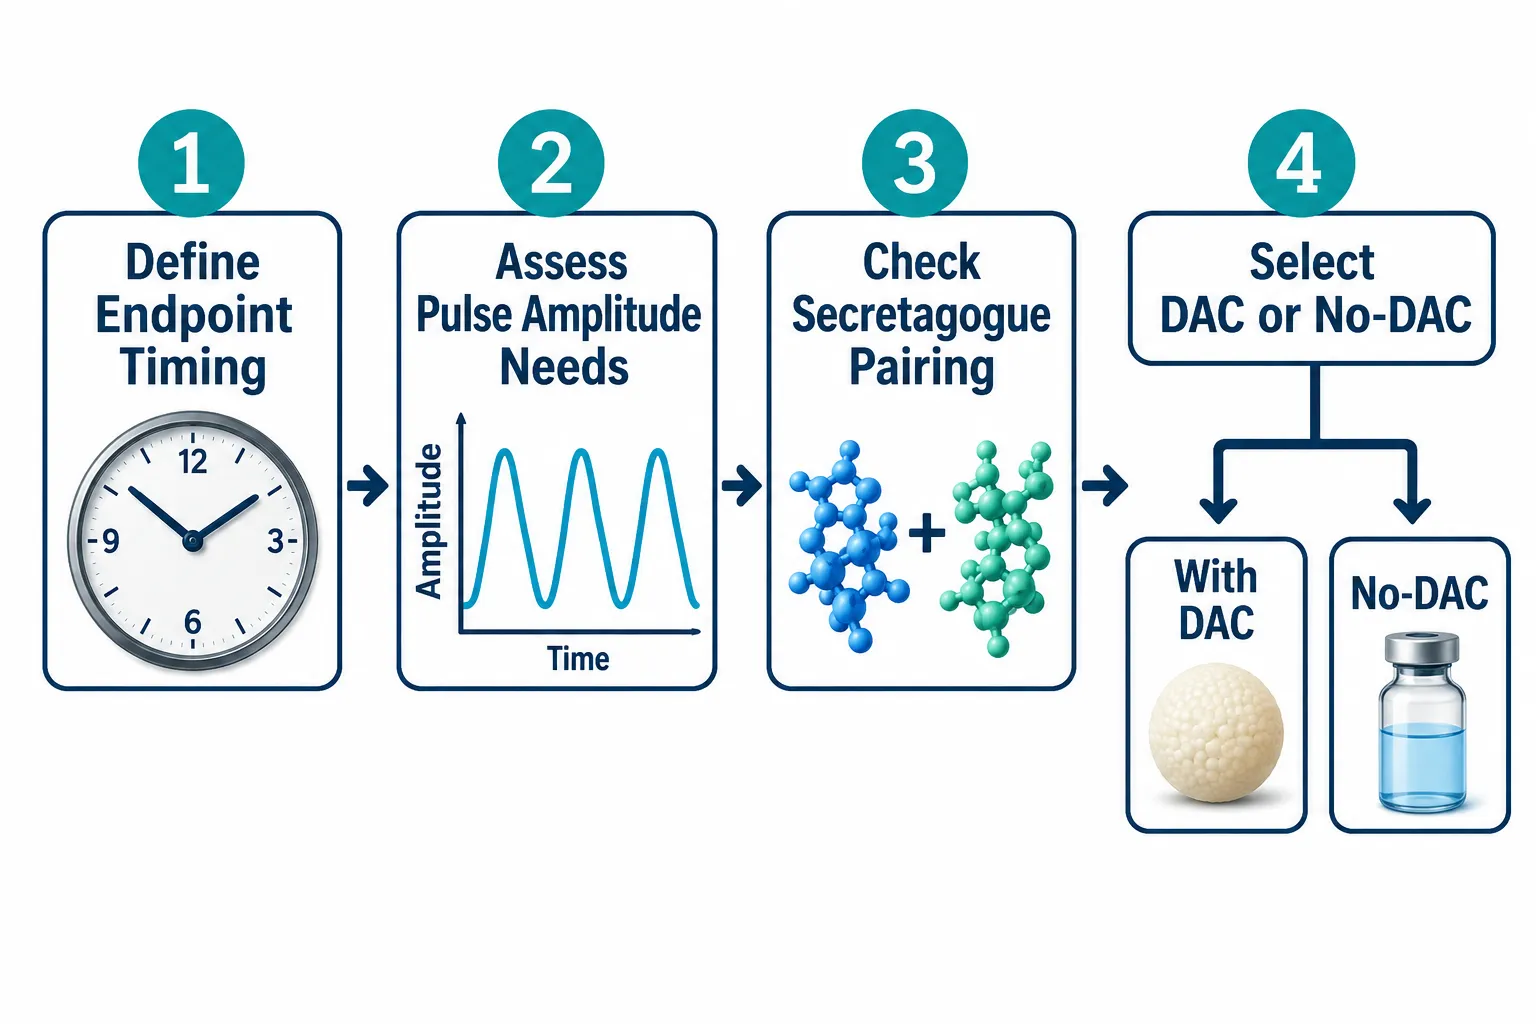
When to use CJC-1295 without DAC (Mod GRF 1-29):
- Pulsatile GH secretion studies requiring discrete, timeable events
- Co-administration with ghrelin mimetics where pulse amplitude synergy is the endpoint (see Sermorelin Ipamorelin CJC-1295 combination research)
- Short-term protocols where baseline drift would confound interpretation
- Studies requiring multiple dosing events per day to replicate physiological pulse frequency
When to use CJC-1295 with DAC:
- Multi-day IGF-1 elevation studies where frequent injections are impractical
- Endpoints measured at 48-96 hour intervals
- Research into tonic GHRH receptor stimulation effects
- Protocols modeling sustained anabolic or metabolic exposure
Researchers working with multi-peptide blend formulations, such as Tesamorelin CJC-1295 Ipamorelin 12mg blend configurations, should confirm which CJC-1295 variant is present before making endpoint timing decisions, as the formulation directly determines whether the GH profile is pulsatile or sustained.
"The formulation is the experiment. Choosing DAC or no-DAC without reference to sampling strategy, baseline behavior, and endpoint timing is not a minor procedural detail, it defines what the data can and cannot show."
Accumulation and Safety Considerations
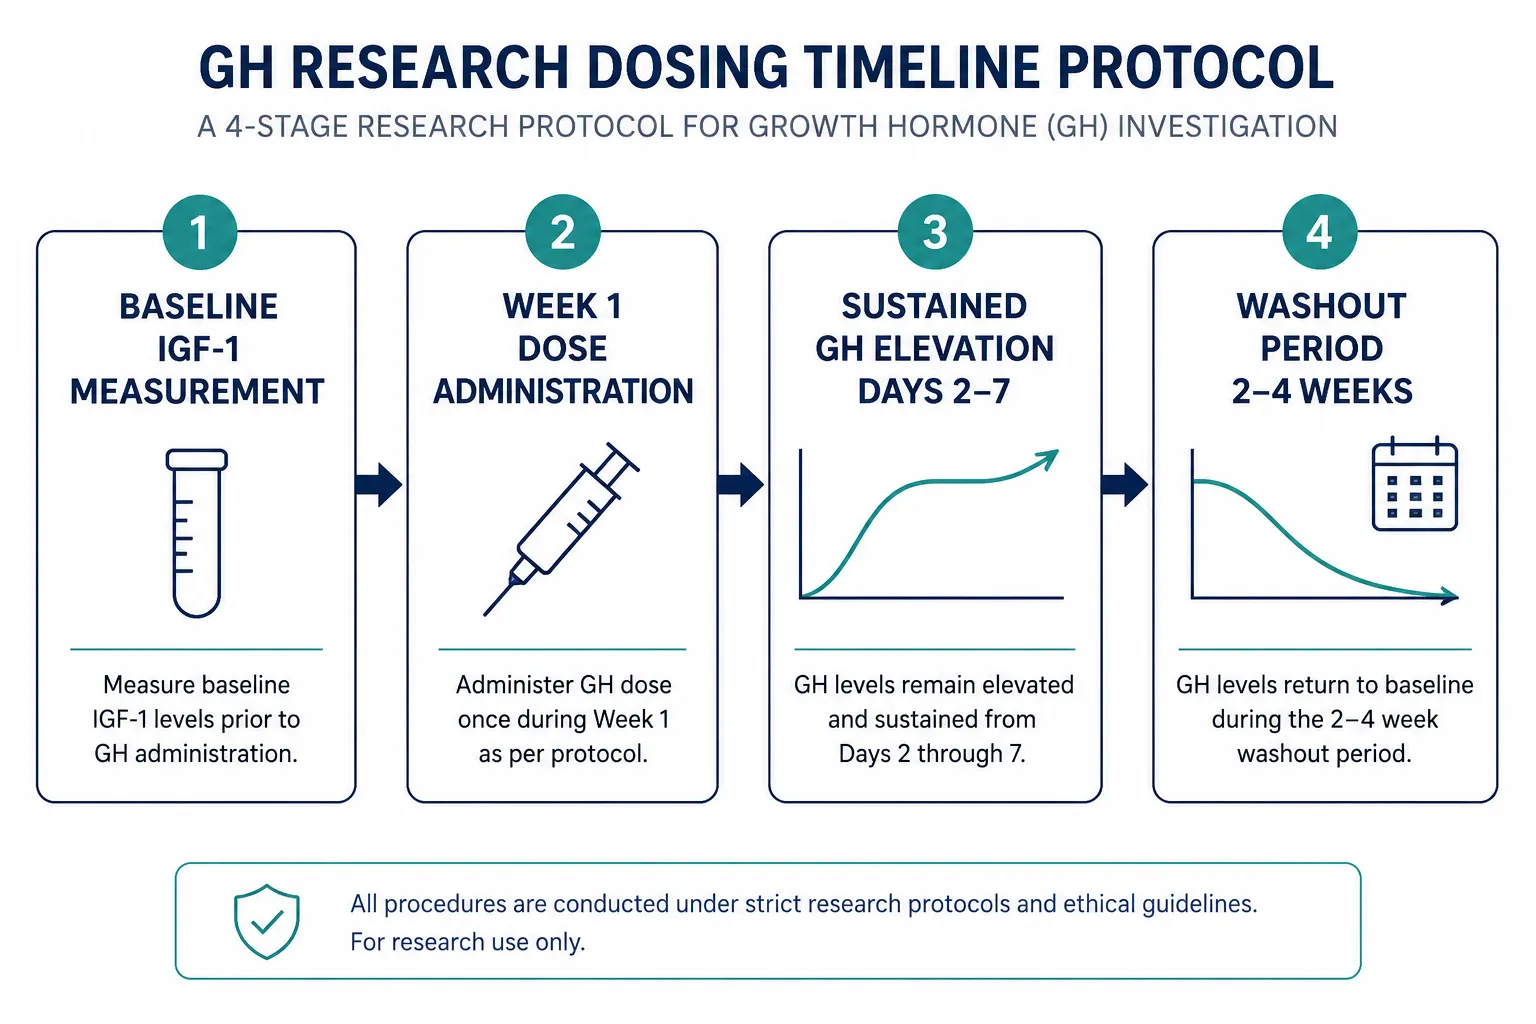
The DAC form's prolonged action raises accumulation concerns in extended protocols. Because each dose adds to residual circulating levels before full clearance, weekly dosing can produce progressive IGF-1 elevation beyond intended exposure levels. No-DAC administration carries a sharply lower accumulation risk given its rapid clearance between doses. Researchers designing multi-week protocols should factor this into inter-dose interval decisions.
Conclusion
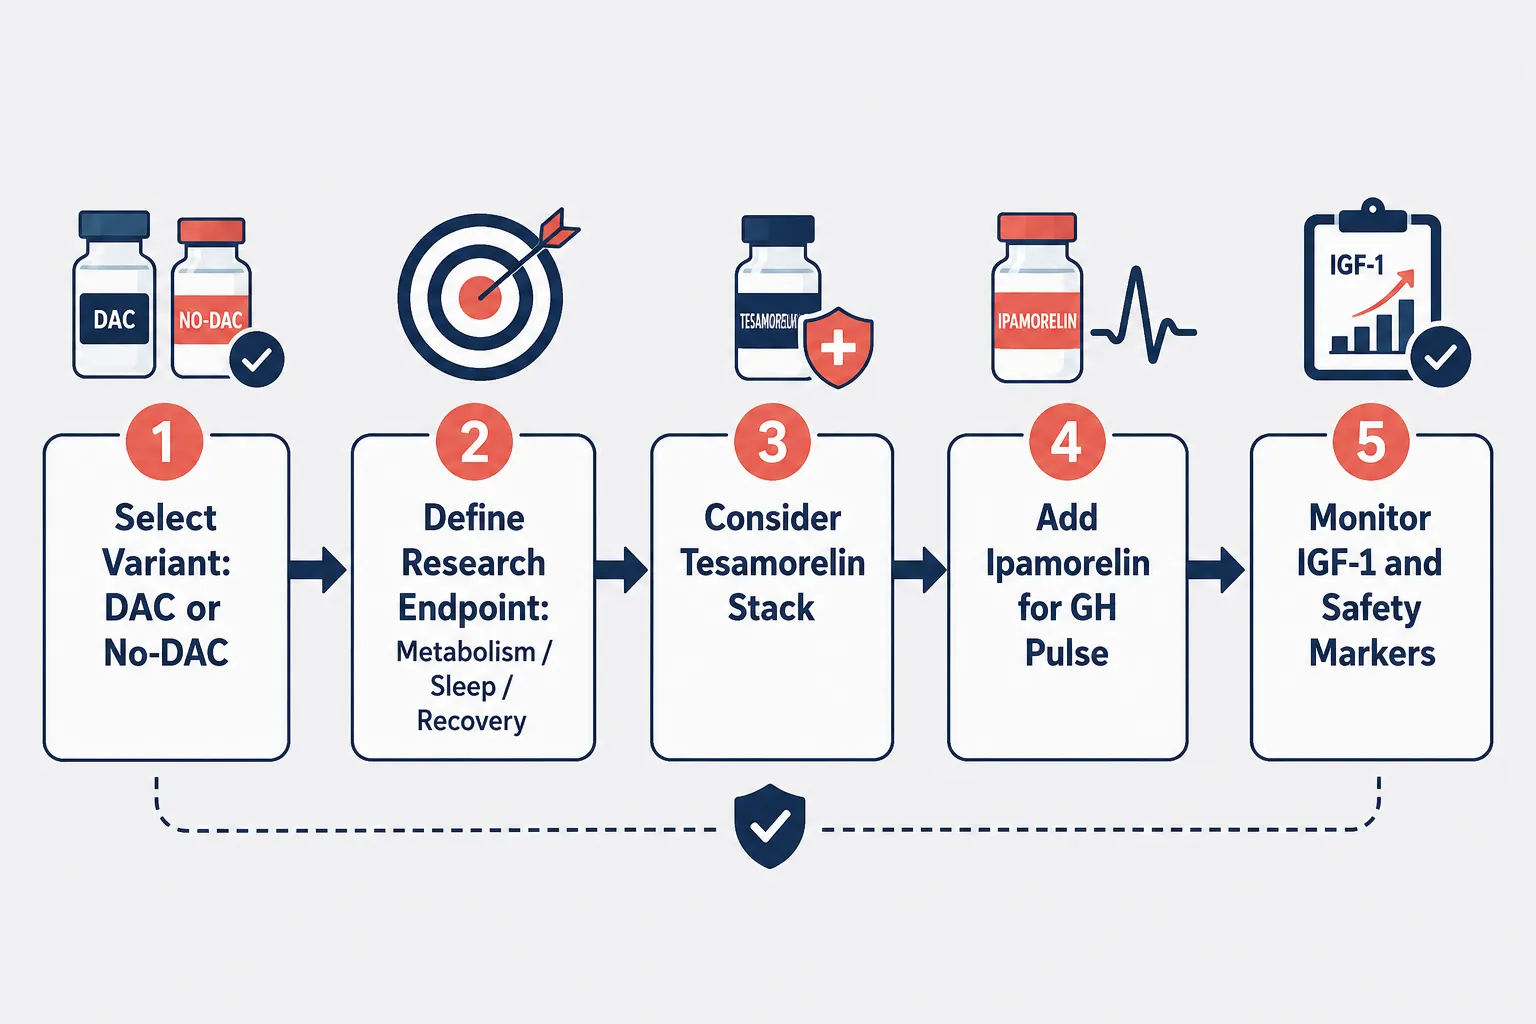
The CJC-1295 With DAC vs Without DAC: Which Research Formulation Fits Pulsatile or Sustained GH Experiments? decision is a structural one that should be made before the experimental protocol is finalized, not after. Use the five-variable selection matrix (sampling density, receptor exposure, baseline drift, pulse amplitude, endpoint timing) as the primary decision framework rather than relying on half-life figures alone.
Actionable next steps for researchers in 2026:
- Define the primary endpoint first: acute GH pulse measurement or sustained IGF-1 elevation.
- Map the sampling schedule to the pharmacokinetic profile of the chosen formulation.
- When co-administering a GHRP-class peptide, default to no-DAC to preserve pulse synergy.
- For multi-day metabolic endpoints, confirm accumulation risk by calculating residual DAC levels at the planned next dose interval.
- Source research-grade material with verified purity to ensure pharmacokinetic assumptions hold, batch-to-batch variability in impure material will corrupt kinetic modeling.
Peptide research continues to evolve rapidly; staying current with CJC-1295 Ipamorelin cycle protocols and updated blend formulations ensures that formulation choices remain aligned with the best available experimental evidence.